



1 | P a g e
Abnormal Psychology: Clinical Psychology Psychopathology
What is Abnormal?
Three key criteria (3Ds):
1. Deviant (PIE: prolonged, inappropriate, and excessive)
2. Dysfunctional or maladaptive and/or
3. Distressful
*Context is important, too!
**Not all abnormal behavior is a diagnosable disorder
Etiology of Abnormal Behavior and/or PsychologicalDisorders
The Biological Approach (physical cause)
● Abnormal behavior patterns represent mental illnesses that have a biological cause
○ Brain abnormalities
○ Neurotransmitter functioning
○ Genetic factors
○ Disease
● Medical Model: Psychological disorders ARE medical diseases with a biological origin. Explain and
treat it as a physical thing.
● Not every disorder has a physical cause that we have identi ed
Etiology of Abnormal Behavior and/or PsychologicalDisorders (subjective experiences)
The Psychological Approach
● An individual’s experiences, thoughts, emotions and personality characteristics contribute to
abnormality.
○ Psychodynamic model: Abnormal behaviors arise from unconscious con icts
○ Behaviorist model: Abnormal behaviors are learned and reinforced
○ Humanistic model: Abnormal behaviors arise from roadblocks on path toward self‐
actualization
○ Cognitive theories: Distorted thinking and maladaptive behavior leads to emotional problems
and more maladaptive behaviors
Etiology of Abnormal Behavior and/or PsychologicalDisorders
The Sociocultural Approach
● Emphasizes social context, including culture
○ Are the cultural norms limiting, oppressive or prejudicial?
○ Social, economic, technological and /or religious in uences
○ Changing cultural norms
● Culture‐related/bound disorders
Etiology of Abnormal Behavior and/or PsychologicalDisorders
THE BIOPSYCHOSOCIAL APPROACH
● Abnormal behavior results from interactions of biological, psychological, and sociocultural factors
● Example: Diathesis‐stress model (aka, vulnerability stress model) ‐
2 | P a g e
○ Diathesis: What is a person's vulnerability or predisposition to developing a disorder?
○ Stress: What is the level of stress the person is experiencing?
Psychological Disorders
● Distinctive patterns of abnormal behavior
○ Also known as “mental disorders” or “mental illnesses”
● Involve disturbances of mood, behavior, thought processes, or perception that result in signi cant
personal distress or impaired functioning
Prevalence of Psychological Disorders
● 50% of people get diagnosed with a mental disorder within their lifetime
Classifying Psychological Disorders
● Diagnostic and Statistical Manual of Mental Disorders (DSM V), 2013 ‐
● Disorders are classi ed by related symptoms
○ Making diagnoses requires clinical judgment, not just checking o the symptoms in the criteria
○ The client’s cultural and social context must be considered; medical and personal history
○ Interaction of nature and nurture
DSM-V Disorder Categories
● Neurodevelopmental Disorders: any intellectual disability, autism (spectrum) dyslexia, ADHD
● Schizophrenia Spectrum and Other Psychotic Disorders: look at severity of system
● BipolarandRelatedDisorders: mood disorder
● DepressiveDisorders: mood disorder
● AnxietyDisorder
● Obsessive‐Compulsive and Related Disorders
● Trauma andStressor‐ ‐Related Disorders
● DissociativeDisorders: Freud based, dissociative identity disorder
● SomaticSymptomDisorders: feel sick with no physical sickness
● Feeding and Eating Disorders
● Elimination Disorders: bed wetting
● Sleep‐WakeDisorders
● Sexual Dysfunctions: not physically caused
● Gender Dysphoria: if being transgender is causing stress
● Disruptive,ImpulseControl and Conduct Disorders: oppositional de ant disorder, klepto disorder
● Substance Use and Addictive Disorders
● NeurocognitiveDisorders: alzhimens, dementia
● PersonalityDisorders: 10 speci c, patterns of behavior, can’t ex personality depending on situation,
antisocial, sociopath, least treatable
● ParaphilicDisorders: pedophillia
● Other...(medicalor medication induced) ‐
Pros and Cons of Diagnostic Labels

●
Rosenhan Experiment; Test e ectiveness of diagnostic labels
Psychology and the Legal System
● Law and psychology are two separate disciplines, but have much in common.
○ Psychology’s goal is to understand behavior
○ The law’s goal is to regulate it
○ Both elds make assumptions about what causes people to act the way they do.
● Con dentiality(unless you put yourself or someone else in danger)
● Insanity defense vs. diminished capacity we do not call people insane only legal people do, we use
proper diagnost ic
Psychological Disorders: Neurodevelopmental Disorders,Neurocognitive
Disorders, Schizophrenia Spectrum & Other Psychotic Disorders
What is “comorbidity”?
● The simultaneous presence of two or more diseases or medical conditions in a patient.
○ Direct: one condition literally causes the other
○ Indirect: indirectly caused by symptom of other illness
○ Something Else: biological cause, trauma
● Comorbidities may a ect a patient’s treatment plan and/or prognosis.
Neurodevelopmental Disorders
● Life long, doesn’t get worse but never goes away
● Stuttering & dyslexia
Intellectual Disability (*Replaced Mental Retardation)
● Characterized as mild, moderate, severe or profound
● IQ must be at least 2 standard deviations from the mean (below 70)
● De cits in problem solving, reasoning and/or judgement
○ Conceptual, social and/or practical skills
Attention De cit/Hyperactivity Disorder
● A developmental disability involving short attention span, distractibility, and extreme di culty
remaining inactive for any period
● Diagnosis and treatment of ADHD is controversial
○ Stimulant drugs
Autism Spectrum
(*Includes former diagnosis of Asperger’s
Syndrome) Neurodevelopmental disorder ● ●
Marked by disabilities in:
○ Language acquisition and non verbal communication ‐
○ Social Interaction/reciprocity in conversation
○ Ability to understand another person’s state of mind
4 | P a g e
Severe cases may include self injurious and/or repetitive behaviors ‐
● Level 1: Requiring support
● Level 2: Requiring substantial support
● Level 3: Requiring very substantial support
Autism: Prevalence and Prognosis
● Can be reliably diagnosed as early as 2, but most cases diagnosed at 4 ‐5.
● CDC estimates 1/59 children (2018)
○ 4x more likely in boys
○ Utah higher than average
● Treatments/Supports
○ Early intervention*
○ Risperidone (for irritability)
○ Behavioral management
○ Educational and school based supports ‐
○ Occupational therapy
○ Family therapy
Etiology of Autism
● Environmental
○ Parental age
○ Low birth weight
○ Fetal exposure to valproate
○ Environmental toxins
● Genetic
○ Heritability rates may range from 37 90% ‐
○ Genetic mutation
● High comorbidity rates
○ Intellectual disability
○ Speci c learning disorders
○ Language disorders
○ ADHD
○ OCD
○ Tic disorders (Tourette’s)
○ Anxiety disorders
○ Nutritional de ciencies
○ Epilepsy
Other Neurodevelopmental Disorders include…
Dyslexia
● A reading disability, thought by some experts to involve a brain disorder

●
● The English language may be part of the problem with 1,120 ways to spell only 40 sounds! —
Current treatment is reading programs which emphasize matching sounds to letter combinations

Tourette’s Syndrome
● Characterized by repetitive, stereotyped, involuntary movements and vocalizations called tics.
● Tics can be simple or complex
● Stress can trigger symptoms
Disorders a ecting cognition…*come back to class 4/7
Neurocognitive Disorders
● Neurocognitive disorders can a ect memory, attention, learning, language, perception, and social
cognition. They may interfere signi cantly with a person’s everyday independence and/or ability to
function.
Major or Minor Neurocognitive Disorders (Dementia)
Etiology = the cause, set of causes, or manner of causation of a disease or condition.
Treatment options
Schizophrenia Spectrum & Other Psychotic Disorders
● Characterized by the following key symptoms:
○ Delusions
○ Hallucinations
○ Disorganized thinking and/or speech
○ Disorganized or abnormal motor behavior
○ Positive and negative symptoms (less observable)
■ at a ect
● Persons are diagnosed according to the number and severity of symptoms
Schizophrenia
● Severe end of the spectrum
● Most closely corresponds to popular notion of insanity or madness
○ Word comes from Greek roots meaning “split brain”
● A ects about 1:100
● Must exhibit two of the following symptoms for at least 6 months:
○ Delusions
○ Hallucinations
○ Disorganized speech
○ Disorganized/abnormal
○ behavior
○ Negative symptoms
● AND Social/Occupational impairment
Schizophrenia Spectrum & Other Psychotic Disorders
Schizotypal (Personality) Disorder
● Mild end of the Schizophrenia spectrum

●
● Cognitive distortions, eccentricities
Schizoa ective Disorder
● Bridge between Bipolar and Schizophrenia; has both the mood disorder and psychotic
symptoms Catatonia
● Waxy exibility, negativism, posturing, mimicking, lack of response, agitation, grimacing,
repetitive movements, catalepsy, stupor
Delusional Disorder
● Delusion without marked impairment in areas of functioning
Schizophreniform/Brief Psychotic Disorder
Etiology of Schizophrenia
● Genetic factors
● Biochemical imbalances
● Brain abnormalities
● Psychosocial in uences
○ Stressful life experiences
○ Diathesis‐stress model
Anxiety, OCD, Depressive, and Bipolar Disorders
What is anxiety disorder?
● A psychological disorder characterized by excessive or inappropriate anxiety reactions
○ Anxiety refers to anticipation of a future concern and is more associated with muscle
tension and avoidance behavior.
○ Fear is an emotional response to an immediate threat and is more associated with a ght or ight
reaction either staying to ght or leaving to escape danger. –
● Must be excessive and prolonged
● You can be diagnosed with more than one at a time.
Generalized Anxiety Disorder
● Persistent anxiety not tied to any particular object or situation
● Anxiety has a “free- oating” quality
● Key feature is excessive worry
Panic Disorder (with or without panic attack)
● Person experiences sudden episodes of sheer terror called panic attacks
● Panic attacks involve physiological symptoms
● Over time, panic attacks can be associated with speci c situations
Phobias
● An irrational or excessive fear of some object or situation Types of phobic disorders: ●
○ Social Anxiety Disorder: Intense fears of social interactions
○ Speci c Phobia: Excessive fears of speci c situations or objects

● Agoraphobia: Excessive, irrational fear of being in public places
Obsessive-Compulsive Disorder (categorie)
● Person experiences persistent obsessions and/or compulsions
○ Obsessions: Nagging, intrusive thoughts person feels unable to control
○ Compulsions: Repetitive behaviors or rituals the person feels compelled to perform
repeatedly
● Anxiety is often an accompanying symptom of obsessive-compulsive disorders
Obsessive-Compulsive Disorder
● Obsessive-Compulsive Disorder ● Body Dysmorphic Disorder
○ Preoccupied with perceived defects or aws in physical appearance
● Hoarding
○ Accumulation of items, preventing the normal use of space
● Trichotillomania (pulling out hair) and Excoriation
Potential Causes of these Disorders
● Biological factors
○ Disturbances in neurotransmitter functioning (chemical imbalances)
○ Genetic in uences / predispositions
● Psychological factors
○ Classical and operant conditioning
● Cognitive factors
○ Misperception or misinterpretation of situations
Depressive Disorders
● Major depressive disorder
○ Persistent depressed mood (6 months), rumination
○ Feelings of worthlessness
○ Changes in sleep, appetite
○ Lethargy, loss of interest, concentration
● Persistent Depressive Disorder (Dysthymic disorder)
○ Depressed most days/most of the day for over a 2 year period
● Premenstrual Dysphoric Disorder (PMDD)
Bipolar Disorders
● Bipolar Disorder (I or II): Person shifts between manic/hypomanic episodes and periods of
depression with intervening periods of normal mood
○ Mania (I)-super high energy vs. hypomania (II)-not as seve re
○ Used to be called “Manic-depression”
● Cyclothymic disorder: Characterized by milder mood swings than bipolar disorder Causes of
Depressive/ Bipolar Disorders
Classic Psychodynamic Theory: Depression is anger turned inward against self

●
● Behavioral Model: Depression results from changes in reinforcement levels
● Cognitive View: How people interpret events contributes to emotional disorders
○ Aaron Beck: One is prone depression if adopt a negatively biased or distorted way of
thinking
● Learned helplessness model (Seligman)
○ Depression results from belief that one is helpless to control reinforcements Depressive ●
Attributional Style: How are negative events explained?
○ Internal not external attribution
○ Global not speci c attribution
○ Stable not unstable attribution
● Chemical imbalances in brain involving the levels or activity of neurotransmitters
● Hereditary in uences
● Stress
Trauma - and Stressor Related, Dissociative, and SomaticSymptom
DisordersClinical Psychology
Trauma- and Stressor-related Disorders
● A traumatic or stressful event has precipitated the onset on symptoms
● A stress disorder occurs when an individual has di culty coping with or adjusting to a recent stressor.
○ Some stressors involve traumatic events or situations in which a person is exposed to actual
or threatened death or serious injury.
● Can experience both:
○ Internalizing symptoms, i.e. anxiety, depression, withdrawal
○ Externalizing symptoms, i.e. anger, aggression, acting out
Posttraumatic Stress Disorder
● PTSD may occur in people who have experienced or witnessed a traumatic event such as a natural
disaster, war/combat, or sexual assault, or who have been threatened with death, sexual violence or
serious injury.
● Symptoms of PTSD fall into four categories. Speci c symptoms can vary in severity.
○ Intrusion
○ Avoidance
○ Alterations in cognition and mood
○ Alterations in arousal and reactivity
Trauma and Stress Related Disorders
● Reactive Attachment Disorder
○ Usually occur as a result of abuse/neglect
○ Emotional withdrawal or inhibition toward caregivers, limited positive a ect, and rarely seeks
or responds to comfort when stressed

Adjustment Disorders
○ Occur following a signi cant life stressor
○ Disturbances of mood, anxiety or conduct
Potential Etiology of Trauma and Stress-related Disorders
● Biological factors
○ Disturbances in neurotransmitter functioning (chemical imbalances)
○ Genetic in uences / predispositions
● Psychological factors
○ Classical and operant conditioning
● Cognitive factors
○ Misperception or misinterpretation of situations
Dissociative Disorders
● The DSM-5 de nes dissociation as “a disruption and/or discontinuity in the normal integration of
consciousness, memory, identity, emotion, perception, body representation, motor control and
behavior”
○ Problems with memory or changes in consciousness or self-identity
○ Inability to maintain a cohesive sense of self, resulting in unusual or bizarre behavior
● There are 5 symptom clusters:
○ depersonalization
○ derealization
○ dissociative amnesia
○ identity confusion
○ identity alteration
Dissociative Identity Disorder (DID)
● Dissociative Identity Disorder (DID): Two or more distinct personalities exists within same
individual Commonly c○ alled “multiple” or “split personality”
● It is now acknowledged that these dissociated states are not fully mature personalities, but rather they
represent a disjointed sense of identity.
○ “Host” personality
Other Dissociative Disorders
● Dissociative Amnesia
○ Loss of memory about self or life experiences
■ Dissociative fugue(travel)
○ No physical cause for amnesia
○ Memory lost usually involves a stressful or traumatic event
● Dissociative Fugue (Psychogenic Fugue)
○ Loss of awareness, AND Traveling or wandering for unknown reasons or without realizing
you have been doing it

●
Etiology of Dissociative Disorders
Anxiety and/stress → Dissociation
● Role of traumatic experiences
○ Childhood trauma and/or abuse
○ Psychological pain or con ict
○ PTSD
● Is DID a genuine disorder?
○ Misdiagnoses?
○ Inadvertently cued by therapists?
Somatic Symptoms and Related Disorders
● Person has physical ailments or complaints that cannot be explained by organic causes OR has an
overor under- reaction to real or unreal medical conditions
● Psychological problems manifesting as physical problems
● Somatic Symptom Disorder
○ Symptoms cause signi cant disruptions in functioning, excessive time devoted to thinking
about or acting on symptoms
● Conversion Disorder
○ Loss of functioning, feeling, or movement in speci c body part
○ Lack of concern with symptoms (La belle indi érence)
○ Way of avoiding anxiety associated with stressful situation
● Hypochondriasis
○ Preoccupied with idea of health problems
○ Excessive worries about disease
○ Anxiety may cause symptoms being experienced
● Factitious Disorders
○ Deliberately producing, feigning, or exaggerating symptoms
○ Munchausen's
○ Munchausen’s by proxy
Etiology of Somatoform Disorders
● Freud: Hysterical symptoms are indications of unconscious con icts
● Learning theories: Symptoms help person avoid painful or anxiety-evoking situations ○
Reinforcement for the “sick” or “caregiver” roles
● Cognitive theorists: Cognitive biases lead to misinterpreting bodily symptoms; anxiety Risk factors ●
for developing somatic symptom disorders:
○ Substance abuse
○ Neglect during childhood
○ Physical and/or sexual abuse
○ Chaotic lifestyle/trauma

○ Chronic illness during childhood
○ Presence of other psychiatric disorders, especially anxiety or depression

Feeding & Eating, Substance & Addictive, and Personality Disorders
Feeding & Eating Disorders
● Act of eating is abnormal, not getting nutrients and is damaging your health, mindset or relationship
● Anorexia nervosa
○ Self starvation, dangerously low body weight
● Bulimia nervosa
○ Binge eating followed by purging (throwing up, laxatives, excessive exercise)
● Binge-eating disorder
○ Repeating binge eating episodes
● Pica
○ Eating non nutritive, nonfood substances
Etiology of Eating Disorders
● Psychological factors
○ Issues of control and perfectionism
○ History of abuse or family con ict
○ Distorted body image
■ Body Dysmorphia
● Biological factors
○ Disturbances in brain mechanisms controlling hunger and satiety; metabolic disorders ○
Irregular serotonin activity
● Environmental/Cultural factors
○ Pressure for unrealistic standards of thinness
○ Dieting as a normative eating pattern
Substance & Addictive Disorders
● Substance Use Disorders
○ Recognizes 10 separate classes of drugs (Ca eine, Opioids, Depressants ect..)
● Substance Induced Disorders
○ Intoxication and/or Withdrawal
○ Substance-induced mental disorder
● Gambling Disorder (only behavioral addiction disorder)
● Diagnostic Criteria
1. Impaired control over use
2. Attempts to reduce or stop use have been unsuccessful
3. Excessive time spent obtaining, using and/or recovering; daily activities revolve around use
4. Intense cravings
5. Social and obligational impairment (work, school, home); social withdrawal
6. Risky behaviors
7. Tolerance & withdrawal

Etiology of Substance & Addictive Disorders
● Psychological Factors
○ Distorted thinking, judgment and decision-making
○ Self-medicating
● Biological Factors
○ Genetic predisposition
○ Changes in brain functioning; reward system (dopamine)
○ Arises out of legitimate illness; injury
● Environmental/Cultural Factors
○ Access
○ Social acceptance
○ Stress
○ History of abuse Personality
Disorders
● Long-term, in exible patterns of behavior and inner experiences that di er signi cantly from what is
expected/normal.
● Usually begin by late adolescence/early adulthood and causes distress and/or problems in
functioning.
● Personality disorders a ect at least two of these areas:
● Way of thinking about oneself and others
● Way of responding emotionally
● Way of relating to other people
● Way of controlling one’s behavior
● There are 10 recognized personality disorders in the DSM- Organized into 3 Clusters: V
○ Odd or Eccentric
■ Paranoid personality disorder Schizoid personality disorder Schizotypal disorder ■ ■
○ Erratic or Emotional
■ Antisocial personality disorder ■ Borderline personality disorder Histrionic ■
personality disorder ■ Narcissistic personality disorder
○ Anxious or Fearful
■ Avoidant personality disorder Dependent personality disorder ■ ■ Obsessive-
compulsive personality disorder
○ These disorders are considered treatment resistant*
Complications of Personality Disorders
● People with a personality disorder are at high risk of behaviors that can lead to physical illness (such
as
● alcohol or drug addiction); self-destructive behavior,
● reckless sexual behavior, hypochondriasis, and clashes with society's values.

● They may develop a mental health disorder; the type (for example, anxiety, depression, or psychosis)
depends in part on the type of personality disorder.
● They are less likely to follow prescribed treatment; even when they follow the regimen, they are
usually less responsive to drugs than most people are.
● They often have a poor relationship with professionals because they refuse to take responsibility for
their behavior or they feel overly distrustful, deserving, or needy
Etiology of Personality Disorders
● Genetics. Researchers are beginning to identify some possible genetic factors behind personality
disorders.
○ One team, for instance, has identi ed a malfunctioning gene that may be a factor in
obsessive-compulsive behaviors.
○ Other researchers are exploring genetic links to aggression, anxiety and fear.
● Childhood trauma/neglect. Studies of personality disorders o er clues about the role of childhood
experiences.
○ One study found a link between the number and type of childhood traumas and the
development of personality disorders.
○ Dysfunctional home or social environments ●
Verbal abuse. Even verbal abuse can have an impact.
○ Children who had experienced verbal abuse were signi cantly more to develop a personality
disorder
● High reactivity. Sensitivity to light, noise, texture and other stimuli may also play a role.
○ Overly sensitive children are more likely to develop shy, timid or anxious personalities.
Psychotherapy (non medical therapy)
What is Therapy?
● Therapy = any treatment process; in psychology/psychiatry, techniques and medical treatments
aimed at dealing with mental disorders and life issues
● Therapy for psychological disorders takes a variety of forms, but all involve some relationship
focused on improving a person’s mental, behavioral, or social functioning
● People enter therapy when they have a problem that they are unable to resolve by themselves ○
Access issues include nances, location, nature of certain disorders, etc. ○
Goals of Therapy
● The therapeutic relationship
● Goals:
○ Identifying the problem

○
Identifying the causes and/or conditions maintaining the problem
○ Deciding on and carrying out some form of treatment
Mental Health Professionals
● Clinical psychologists
○ Doctoral degree in psychology, licensing exam
○ Psychological testing, diagnosing mental disorders, psychotherapy ○
*Psychoanalysts
● Counseling psychologists
○ Doctoral degree in psychology, licensing exam
○ Counseling for milder range of problems, such as di culties adjusting to major/minor life
changes
○ Many are found in school/college settings
Mental Health Professionals
● Psychiatrists
○ Medical degree, residency
○ Physicians specializing in diagnosis and treatment of mental illness
○ May prescribe psychiatric drugs or practice psychotherapy
● Clinical or psychiatric social workers
○ Master’s degree in social work
○ Help individuals with severe mental illness to receive services from community agencies and
organizations
Mental Health Professionals
● Counselors
○ Master’s degree in counseling eld
○ Varied settings and types of counseling
○ Pastoral counselors
● Psychiatric nurse practitioner
○ R.N. with master’s degree in psychiatric nursing
○ Working with people who have severe psychological disorders
● Modern Therapy
● Biopsychosocial Model
○ Interaction of nature/nurture
○ Role of culture
● Variety of therapies to choose from
○ Psychological therapies
○ Biomedical therapies
Types of Psychotherapy *come back to class 4/21*

● Insight Therapy: Talk therapy, dream analysis, hypnosis. Gaining insight into causes of problem ○
Psycho- dynamic therapies
■ Freudian
■ Neo- Freudian
○ Humanistic Therapies
○ Cognitive Therapies
● Behavioral Therapy: doesn’t care about why the issue occurs, just tries to x behavioral issues
○ Based on Operant Conditioning
○ Based on Observational Learning
○ Based on Classical Conditioning
● Cognitive Behavioral Therapy: combo of both Insight Therapy and Behavioral Therapy Group ○
Therapy
Types of Psychotherapy
Insight Therapy: Psychoanalysis
Basis: Problems arise from tension created in the unconscious mind by impulses and threatening memories
Developed by Sigmund Freud in the early 20th century.
This is where the image of the patient lying on the couch, facing away from the therapist comes from the --
goal is for the patient to be removed from the therapist a bit; not face- -face - Freud believed this would to
allow them to speak more openly.
Purpose: Attempt to reveal and interpret the contents of the unconscious mi ; By bringing these issues into nd
consciousness, they would be rendered harmless.
Techniques:
Free association
Dream analysis
Projection (such as Rorschach tests)
Hypnosis
Analysis of transference
Insight Therapy: Humanistic Therapies
Basis: People strive for positive growth and self-actualization, but may be blocked by an “unhealthy
environment”.
● An “unhealthy environment” might include low self-esteem, feelings of alienation, failure to achieve
goals, criticism by others, unhealthy relationships, or a general dissatisfaction with life.
● Uses the term client, rather than patient, to avoid a negative or “sick” connotation.
● Client-Centered Therapy Carl Rogers, developed by , seeks to create a nurturing environment;
The therapist must exhibit genuineness, empathy and unconditional positive regard.
● Purpose: Remove the self-actualization. roadblocks to
● Techniques:
○ Enhancing self-esteem & self-e cacy
○
○ Helping the client to set and realize goals
Re ection of feeling: help clients understand the emotions they’re feeling by paraphrasing
clients words and repeating it back to them--attempting to capture their words and tone, so they can “hear”
how they sound and what they are saying, so that they can re ect on it. Insight Therapy: Cognitive
Therapies
Basis: Errors in thinking cause mental illness and emotional distress.
● Negative and unrealistic cause us distress and result in problems. When a person su ers with
psychological distress, the way in which they interpret situations becomes skewed, which in turn has
a negative impact on the actions they take.
● Purpose: Confront destructive thoughts and irrational beliefs.
● Techniques:
○ Help people to develop alternative ways of thinking and healthy coping strategies, aiming to
reduce their psychological distress.
● The 3 C’s of Cognitive Therapy
○ Catch: Identify the thought that came before the emotion.
○ Check: Re ect on how accurate and useful the thought is
○ Change: Change the thought to something more accurate or useful
Beck’s Cognitive Therapy
● Aaron Beck believes that a person’s reaction to speci c upsetting thoughts may contribute to mental
illness. As we confront the many situations that arise in life, both comforting and upsetting thoughts
come into our heads. Beck calls these unbidden cogni automatic thoughts. tion’s
● When a person’s stream of automatic thoughts is very negative you would expect a person to
become depressed (I’m never going to get this essay finished, my girlfriend fancies my best friend, I’m getting fat,
have no money, my parents hate me - have you ever felt like this?) Quite often these negative thoughts will
persist even in the face of contrary evidence.
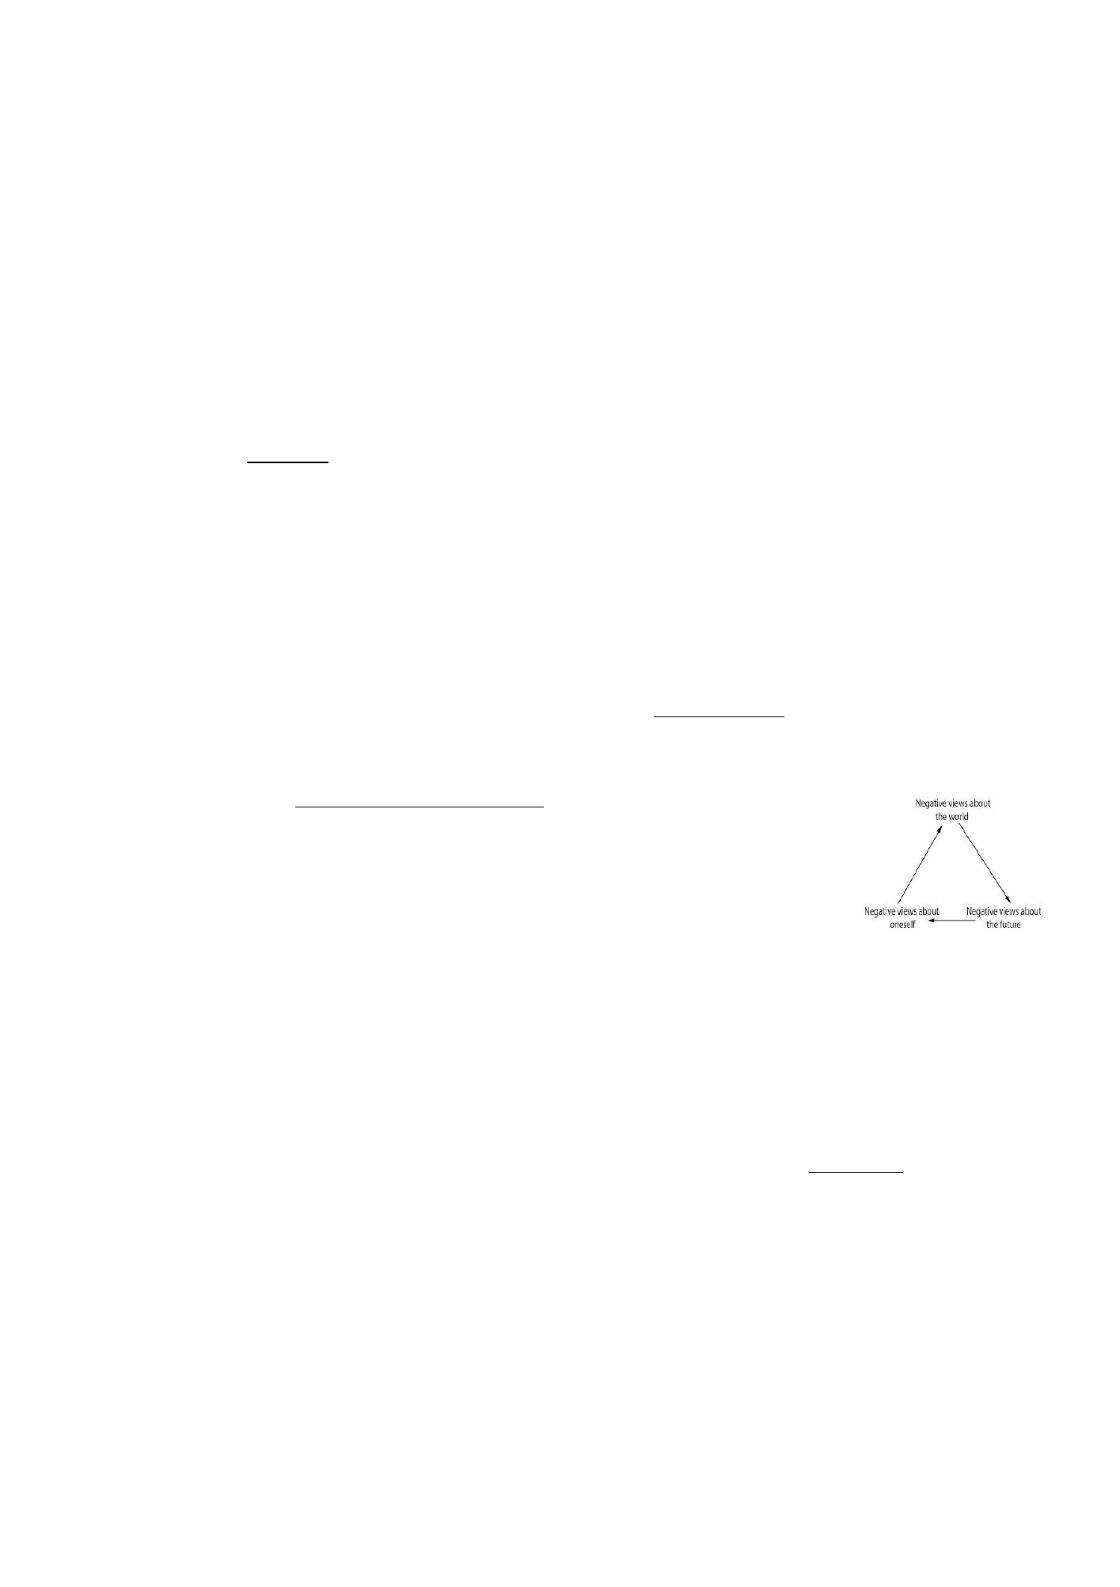
● Beck (1967) identi ed three mechanisms that he thought were responsible for depression:
○ The negative cognitive triad (see image)
○ Negative self schemas
○ Errors in Logic (i.e. faulty information processing)
Behavior Therapy: Behavior Modi cation
Basis: Behaviors are learned, and can be unlearned/replaced.
● Used when a troublesome behavior/action is the cause or contributing to the mental health problem.
● Purpose: Problems deemed “learned by association” can be “unlearned by association” -
CLASSICAL
CONDITIONING
● Techniques:
○ Counterconditioning: Weakening or eliminating an undesired response by introducing and
strengthening a new, incompatible response.
○ Systematic Desensitization: Used primarily with anxiety and phobias, uses visualizations of
feared objects/situations to overcome their anxiety. (Identified by Joseph Wolpe)

■ Create a “fear hierarchy” and move from least to most feared, with the therapist
calming/supporting the client at each level.
○ Exposure Therapy: Same idea, but actually exposing them to their feared object/situation
(rather than visualizing).
○ Aversion Therapy: present clients with the situation/behavior they are trying to change, and
then present an unpleasant stimuli, which they will begin to associate with the undesirable
behavior
Mary Cover Jones - “The Mother of Behavioral Therapy”
● Counter- conditioning
Behavior Therapy: Contingency Management
Basis: Behaviors are learned, and can be unlearned/replaced.
● Purpose: Altering consequences (reinforcements/punishments); Being very careful to ensure we are
actually reinforcing those behaviors that are acceptable/appropriate, and NOT those we want to
change
- OPERANT CONDITIONING (B.F. Skinner)
● Replace problem behaviors with positive alternatives.
● Techniques:
○ Token Economy: Individuals are given “tokens” (points, fake money, tickets, etc.) for desirable
behaviors, which can later be exchanged for privileges, prizes, food, etc. (like a chore chart)
■ Used in schools, prisons, mental hospitals, etc. Reinforces good behavior, but does not
really punish bad behavior – the idea is that the good will replace/outweigh the bad.
○ Participant Modeling: Observe the desirable behaviors of others, and see their
reinforcement; encourages imitation.
Cognitive-Behavioral Therapy
● Cognitive behavioral therapy (CBT)can be used to treat people with a wide range of mental health
problems. CBT is based on the idea that how we think (cognition), how we feel (emotion) and how
we act (behavior) all interact - Speci cally, our thoughts determine our feelings and our behavior.
○ Aimed at modifying both cognitions and behaviors
○ A combination of insight + behavioral therapy ●
Techniques:
○ Modify irrational/negative self-talk
○ Set reasonable behavioral goals and reinforce them ○
Develop realistic strategies for change and develop new skills Albert ●
Wllis - Rational Emotive Behavior Therapy (REBT):
○ Thoughts create feeling => Behavior reinforces thoughts => Feelings create behavior
Group Therapy
Any form of therapy done with more than one client/patient at a time (often humanistic in nature).
● Self-help and/or support groups
● Couples/Marriage therapy
● Family therapy

○
The family/couple, not an individual, is the unit of treatment--though often, one member has been
deemed the “problem”
○ Views Individual problems as symptomatic of relationship breakdown ●
Techniques:
○ Acquire more e ective communication and con ict resolution skills
○ Resolve power struggles
○ Develop support systems
● Pros: less costly, practice social skills, share coping strategies/modeling, creates a support system.
● Cons: No one-on-one attention, reluctance to disclose, lacks deep exploration of individual issues.
Which Therapy Works???
How e ective is therapy? Individuals surveyed reported:
● Therapy works; it helped lessen or eliminate their problems
● Long-term is better than short-term
● A positive and supportive relationship between therapist/client was the strongest indicator
of success, regardless of the therapy strategy beingused!
Other studies show:
● Behavior therapies seem to have the most bene t on anxiety related problems, are e ective for
substance abuse, autism-related and other neurocognitive disorders.
● Insight therapies seem to be more bene cial for depression, relationship/socialization issues.
● The Cognitive-Behavioral approach works well for eating disorders, agoraphobia, chronic pain, OCD
and depression.
Biomedical Therapies
Antianxiety Drugs/Minor Tranquilizers/ Benzodiazepines (end in AM)
● Also called minor tranquilizers/Benzodiazepines
● E ects
○ Reduces anxiety
○ Produces calmness
○ Reduces muscle tension
○ Slows down brain
● E ect on GABA receptors (inhibits/slows the ow of neurons) makes GABA more sensitive Fast ●
immediate relief
● Side E ects: tired, drowsy, impaired muscle coordination, nausea, at a c:no/late emotional
reaction, addictive, street value. Paradoxical E ect:drug does opposite of what it should do.
● Examples: Valium, Librium, Xanax, Ativan
Antidepressants
● Increases availability of neurotransmitters
○ Serotonin, norepinephrine ●
Not immediate acting

● Major types
○ Selective serotonin-reuptake inhibitors SSRIs: ( neuron releases serotonin from synapse it
blocks the serotonin reuptake allowing serotonin to stay in system longer) (Prozac, Zoloft, – ○
Lexapro, Paxil, Celexa)
○ Monoamine oxidase inhibitors (MAOIs:stronger than SSRI one of the rst antidepressants) –
(Nardil, Phenelzine)
○ Tricyclics: prevent absorption of serotonin (Tofranil, Elavil)
○ Atypical (minor, can take it with SSRI): Wellbutrin, Zyban, E exor, Cymbalta
● Therapeutic bene ts for both depression and anxiety disorders
Antipsychotics
● Sometimes called major tranquilizers
● Reduced amount of people in Mental Hospitals by 50%
● Treatment for schizophrenia, other psychotic
● disorders
● Blocks action of dopamine at receptor sites in
● brain. Issue is not that we need more dopamine but same neuron pathways dopamine is on is where
hallucination comes from.
○ Side e ect: Tardive dyskinesia (Muscle trembles and ticks)
● Examples:
○ Thorazine, Mellaril, Proloxin, Haldol, Clozaril
Other Psychiatric Drugs
Mood stabilizers to reduce mood swings
E.g., Lithium carbonate (Eskalith, Lithobid) or Valproate (Depakote)
Stimulants used to improve attention spans and reduce disruptive behavior in hyperactive children
E.g., Ritalin, Cylert, Adderall, Concerta
Evaluating Psychotropic Drugs
Limitations
May reduce or control symptoms, but not a cure
Does not teach how to resolve problems or develop necessary life skills
Risks of adverse side e ects
Can lead to psychological or physical dependence
Evaluating Psychotropic Drugs
Relapses common when stop taking drugs.
15-20% of schizophrenics relapse even when reliably taking medication
May be seen as a “quick x”
Overperscribed?
Useful for temporary relief
Usually used in tandem with psychotherapy
Other Biomedical Therapies

● Electroconvulsive therapy (ECT) -shocks
● Transcranial Magnetic Stimulation (TMS)- kinda like shocks but magnets, like turning your phone on
and o
● Deep brain stimulation-shock directly into brain
● Psychosurgery
○ Prefrontal lobotomy, performed into the 1950’s don’t do anymore
○ “Split-Brain” for severe epilepsy
○ Newer more speci ed techniques rarely used as a last resort; e.g. bilateral capsulotomy (targeted
brain lesioning, damage parts of the brain)

