


Association Between Childhood Obesity and Cerebral
Palsy, Down Syndrome and Epilepsy or Seizure
Disorder
Section 1: Foundation of the Study and Literature Review
Introduction
Obesity has been identified as a nutrition-related chronic disease (NRCD) that has
increased over the decades and can lead to several other health issues such as diabetes
and coronary heart disease (Sahoo et al., 2015). According to the Centers for Disease
Control and Prevention (CDC, 2021), for children to maintain a healthy body weight,
they must consume nutritional foods and engage in physical activity. Lack of physical
activity, diet, and genetics may cause childhood obesity (Sahoo et al., 2015). Although
there is a plethora of research studies on childhood obesity and its relationship to physical
activity and nutrition, there is a lack of information on the relationship between
childhood obesity and some physical (PD) and intellectual disabilities (ID).
According to Segal et al. (2015), children with disabilities have a 13.4% higher
obesity prevalence rate than children without a disability. Furthermore, Segal et al.
(2015) suggested more research be conducted on childhood obesity and disabilities. This
study will utilize data focusing on childhood obesity archived from the National Survey
of Children’s Health (NSCH) to examine the association between childhood obesity and
the following intellectual and physical disabilities: cerebral palsy (CP), Down Syndrome
(DS), and epilepsy or seizure disorders.

CP is one of the most common childhood disabilities that affects an individual’s
ability to move around, interact, and maintain balance (CDC, 2022). According to Barja
et al. (2020), obesity is an emerging prognostic factor among individuals with CP. Over
the years, the number of overweight children diagnosed with cerebral palsy has increased
(Meyns et al., 2016). Moreover, overweight children diagnosed with CP have trouble
walking (Mudge et al., 2021), which is connected to a lack of physical activity (Mudge et
al., 2021).
Down Syndrome is defined as “a genetic disorder caused when abnormal cell
division results in an extra full or partial copy of chromosome 21” (Mayo Clinic, n.d.).
Children and adolescents diagnosed with Down Syndrome or trisomy 21 are at a higher
risk of being diagnosed as overweight or obese (Foerste et al., 2016). Considering the
BMI and shorter stature of a child with Down Syndrome, they are more likely to be
heavier than a child without Down Syndrome (Basil et al., 2016).
Epilepsy or seizure disorder is “any of various disorders marked by abnormal
electrical discharges in the brain and typically manifested by sudden, brief episodes of
altered or diminished consciousness, involuntary movements, or convulsions”
(MerriamWebster, n.d.). Researchers suggest that there be research conducted for
improved methods to identify the relationship between seizure severity and obesity (Ng
& Hodges, 2020). This study helps to close the gap on childhood obesity and its
association to intellectual and physical disabilities.
This research study aids in preventing childhood obesity among disabled children
whose parents are unaware of the relationship between this health issue and physical and

intellectual disabilities. This study gives health practitioners important information about
healthcare risk factors, disease trends, and functional abilities and disabilities in children.
Moreover, this study focused on disabilities that are associated with obesity that have not
yet been thoroughly studied. Lastly, this study’s potential social change impact is to
decrease morbidity and mortality associated with obesity among youth and children. To
begin this study, Section 1 includes a discussion of the problem of the study, the purpose
of the study, research questions and hypotheses, theoretical framework, nature of the
study, literature review related to key variables, definitions, limitations, the significance
of the research, and the summary and conclusion.
Problem Statement
According to the CDC, childhood obesity is an ongoing public health issue
causing poor health among children and adolescents (CDC, 2021). The prevalence rate
of childhood obesity in the U. S. was 49.7% amongst children ages 2-19 between
20112014 (CDC, 2021). Over 13.5 million children in the United States live with a
determining diagnosis of obesity or being overweight (Imoisili et al., 2019).
Based on the literature review and previous research, there is a relationship
between an overweight child and a physical or intellectual disability, specifically cerebral
palsy, Down Syndrome and epilepsy or seizure disorder. Socioeconomic factors, lack of
physical activity, environmental factors, and psychological factors are also associated
with childhood obesity. The many concerns for overweight children with a disability
include the inability to walk and or do things independently, increased risk of sleep
disturbances such as obstructive sleep apnea, heart conditions, and complications from

the medicine consumed for their disability. Other concerns are serious health issues that
could lead to death in overweight children with an ID or PD. Lastly, the problem is that
there are 49.7% of overweight children at risk for health conditions leading to mortality
(CDC, 2021).
Socioeconomic factors such as the parents’ income and education levels, and the
child’s age, sex, and race may influence a child’s weight status. According to researchers
Jin & Jones-Smith (2015), of the participants in their study, children living in a
household with lower income were at a higher rate of obesity than children living in a
household with higher income. Another researcher indicated that childhood obesity is
complex and may vary over time according to the child’s race, sex, and Hispanic origin
(Ogden, 2018). Ogden also stated that the head of household’s income and education
level had some effect on the child’s obesity status (2018). The lower the education and
income level, the higher the childhood obesity prevalence rate (Ogden, 2018). More
research should be conducted on the parents’ education level, and the race and age of the
child.
There is a lack of research on lifestyle factors and their relationship with
childhood obesity (O’Shea et al., 2018). Children with these disabilities could experience
a lack of social participation that affects their weight levels, as a lack of desire or
incapability to interact socially could be detrimental to a child’s weight. According to
McPherson et al. (2016), further research is needed to address the understanding of
childhood obesity findings and apply the findings to children who have physical
disabilities. Bertapelli et al. (2016) suggested that further research is needed to address
population-based research regarding the weight and BMI status of a child or youth with

Down Syndrome. Based on the literature, more research should be conducted on
intellectual and physical disabilities and their association with childhood obesity, race
and age of child, and the socioeconomic factors of the parents, such as income and
education level.
Purpose of Study
The purpose of this study is to generate knowledge of childhood obesity and its
relationship to cerebral palsy, Down Syndrome, and epilepsy or seizure disorders, based
on data from the National Survey of Children’s Health collected in 2018-2019. This
study also addressed the number of overweight, intellectually, and physically disabled
children at risk for developing other serious health issues and factors mentioned above.
This cross-sectional study examined the association between overweight children ages
017 and their diagnosis of the following physical and intellectual disabilities: cerebral
palsy, Down Syndrome, and epilepsy or seizure disorder. The confounding variables
explored were the education level and household income of the parents and the age, race,
and sex of the child.
The study provides insight on whether the physical and intellectual disabilities
and the parent’s socioeconomic status affect a child’s weight status. This study also
provides insight to other researchers and healthcare providers regarding if the age or race
of the disabled child affects the child’s weight status. Lastly, this study promotes
childhood obesity prevention in children with physical and intellectual disabilities.

Research Variables and Study Population
The research variables and study population for this cross-sectional research study
are as follows:
Dependent Variable (DV): Childhood Obesity as indicated by a doctor or other
healthcare provider.
Independent Variables (IV): cerebral palsy, Down Syndrome, and epilepsy or
seizure disorder
Confounding Variables (CV): socioeconomic status (SES) of the parent or
guardian, education level of the parent or guardian, income level of the parent or
guardian, as well as the age, race, and sex of the child.
Study Population: Children and adolescents up to age 17, nationwide, African
American, White, Hispanic, and Non-Hispanic children.
Research Questions and Hypotheses
RQ1: Is there an association between childhood obesity and cerebral palsy?
H01: There is no association between childhood obesity and cerebral palsy.
H11: There is an association between childhood obesity and cerebral palsy.
RQ2: Is there an association between childhood obesity and cerebral palsy when
controlling for socioeconomic status of parent, education level of parent, income level of
parent or guardian, and the age, race, and sex of child?
H02: There is no association between childhood obesity and cerebral palsy when
controlling for socioeconomic status of parent, education level of parent, income level of
parent or guardian, and the age, race, and sex of child.

H12: There is an association between childhood obesity and cerebral palsy when
controlling for socioeconomic status of parent, education level of parent, income level of
parent or guardian, and the age, race, and sex of child.
RQ3: Is there an association between childhood obesity and Down Syndrome?
H03: There is no association between childhood obesity and Down Syndrome.
H13: There is an association between childhood obesity and Down Syndrome.
RQ4: Is there an association between childhood obesity and Down Syndrome
when controlling for socioeconomic status of parent, education level of parent, income
level of parent or guardian, and the age, race, and sex of child?
H04: There is no association between childhood obesity and Down Syndrome
when controlling for socioeconomic status of parent, education level of parent, income
level of parent or guardian, and the age, race, and sex of child.
H14: There is an association between childhood obesity and Down Syndrome
when controlling for socioeconomic status of parent, education level of parent, income
level of parent or guardian, and the age, race, and sex of child.
RQ5: Is there an association between childhood obesity and epilepsy or seizure
disorder?
H05: There is no association between childhood obesity and epilepsy or seizure
disorder.
H15: There is an association between childhood obesity and epilepsy or seizure
disorder.

RQ6: Is there an association between childhood obesity and epilepsy or seizure
disorder when controlling for socioeconomic status of parent, education level of parent,
income level of parent or guardian, and the age, race, and sex of child?
H06: There is no association between childhood obesity and epilepsy or seizure
disorder when controlling for socioeconomic status of parent, education level of parent,
income level of parent or guardian, and the age, race, and sex of child.
H16: There is an association between childhood obesity and epilepsy or seizure
disorder when controlling for socioeconomic status of parent, education level of parent,
income level of parent or guardian, and the age, race, and sex of child.
RQ7: Does the education level of the parent or guardian have a moderation effect
on the association between childhood obesity and cerebral palsy, Down Syndrome, and
epilepsy or seizure disorder?
H07: The education level of the parent or guardian does not have a moderation
effect on the association between childhood obesity and cerebral palsy, Down Syndrome,
and epilepsy or seizure disorder?
H17: The education level of the parent or guardian does have a moderation effect
on the association between childhood obesity and cerebral palsy, Down Syndrome, and
epilepsy or seizure disorder?
RQ8: Does the income level of the parent or guardian have a moderation effect on
the association between childhood obesity and cerebral palsy, Down Syndrome, and
epilepsy or seizure disorder?

H08: The income level of the parent or guardian does not have a moderation effect
on the association between childhood obesity and cerebral palsy, Down Syndrome, and
epilepsy or seizure disorder?
H18: The income level of the parent or guardian does have a moderation effect on
the association between childhood obesity and cerebral palsy, Down Syndrome, and
epilepsy or seizure disorder?
RQ9: Does the age of the child have a moderation effect on the association
between childhood obesity and cerebral palsy, Down Syndrome, and epilepsy or seizure
disorder?
H09: The age of the child does not have a moderation effect on the association
between childhood obesity and cerebral palsy, Down Syndrome, and epilepsy or seizure
disorder?
H19: The age of the child has a moderation effect on the association between
childhood obesity and cerebral palsy, Down Syndrome, and epilepsy or seizure disorder?
RQ10: Does the race of the child have a moderation effect on the association
between childhood obesity and cerebral palsy, Down Syndrome, and epilepsy or seizure
disorder?
H010: The race of the child does not have a moderation effect on the association
between childhood obesity and cerebral palsy, Down Syndrome, and epilepsy or seizure
disorder?
H110: The race of the child has a moderation effect on the association between
childhood obesity and cerebral palsy, Down Syndrome, and epilepsy or seizure disorder?

RQ11: Does the sex of the child have a moderation effect on the association
between childhood obesity and cerebral palsy, Down Syndrome, and epilepsy or seizure
disorder?
H011: The sex of the child does not have a moderation effect on the association
between childhood obesity and cerebral palsy, Down Syndrome, and epilepsy or seizure
disorder?
H111: The sex of the child has a moderation effect on the association between
childhood obesity and cerebral palsy, Down Syndrome, and epilepsy or seizure disorder?
Theoretical Framework
The theoretical framework used for this study was the Social Cognitive Theory
(SCT), formerly known as the Social Learning Theory (SLT) (LaMorte, 2019). SCT is a
causational theory that explains psychosocial functioning and includes three aspects:
belief strengthening (observation), improving goals (self-regulation), and competency
building (reciprocal determination) (Bandura, 1988). Since its inception in 1988, the
SCT has added other concepts to the framework, bringing the theory to six concepts. The
six constructs are listed below in Figure 1: reciprocal determination, behavioral
capability, observational learning, reinforcements, expectations, and self-efficacy
(LaMorte, 2019). The SLT began with the first five concepts, and the last concept as
added once the theory was renamed the SCT in 1986 (LaMorte, 2019). As the theory has
improved over the years, it has given more meaning and value to the framework and how
to utilize the theory in different aspects of life.

The SCT has been applied in other research areas such as clinical issues, health
issues, promotional programs, and environmental change (Kelder et al., 2015). The
application of this theory includes the following factors: personal cognitive factors,
socioenvironmental factors, and behavioral factors. The personal cognitive factors
involve the following constructs, self-efficacy, knowledge, and outcome expectations
(Kelder et al., 2015). The socio-environmental factors include observational learning,
normative beliefs, opportunities and barriers, and social support (Kelder et al., 2015). In
contrast, the behavioral factors include behavioral skills, intentions, and reinforcement &
punishment (Kelder et al., 2015). The SCT is the most used theory to promote childhood
obesity prevention (Alexander et al., 2021).
The purpose of using this theoretical framework in this study was to focus on the
environmental and socioeconomic factors of the child and parent or guardian. The SCT
shows how the child’s guardian’s socioeconomic factors, such as the environment,
finances, education level, personal beliefs, etc., can affect the child’s well-being
(Alexander et al., 2021). Bandura’s theory can help determine why people behave the
way they do, according to their age, education level, and other socioeconomic factors
(Knol et al., 2017). The theory could also provide the guardian with goal-setting support
to improve the child’s health. In other words, utilizing the SCT framework for this study
could promote child obesity prevention.
The SCT is a vital framework and is considered one of the most used theories for
published research (Kelder et al., 2015). Self-efficacy is a SCT construct that is essential
for human behavioral changes by recognizing a person’s confidence level (LaMorte,
2019). Due to the dependent variable, childhood obesity, each research question was
applied to the first and last concept of the social cognitive theory model: reciprocal
determination and self-efficacy. I operationalized the SCT in this study to examine how
intellectual or physical disability had the most significant effect on childhood obesity
rates in the United States. The SCT was the best framework to conduct my research
because it related to the quantitative data of the child’s environment, and the quantitative
data of the parents’ socioeconomic factors. Therefore, this model was an effective choice
for this study.
Figure 1
Social Cognitive Theory Model
Perceived
Susceptibility
Perceived
Severity
Perceived
Benefits
Perceived
Barriers
Cue to Action
Self-Efficacy
Note. (LaMorte, 2019)

Another model that was used for this study was the Health Belief Model (HBM).
The six constructs of the HBM are perceived susceptibility, perceived severity, perceived
benefits, perceived barriers, cue to action, and self-efficacy, as illustrated in Figure 2
(LaMorte, 2019). The HBM helps to explain why people fail to adopt disease prevention
strategies and responses to medical treatments and symptoms of an illness (LaMorte,
2019). The HBM explained the person’s feelings and perceptions of their current illness,
or the development of an illness (LaMorte, 2019). Lastly, the HBM stated that a person’s
beliefs and recommended health actions could determine whether the individual will
make the behavioral changes or not.
The HBM was useful for this current study because it identified whether there is
an association or relationship between the dependent variable, childhood obesity, and the
confounding variables, such as the parent or guardians’ income level and education level.
Obesity is a complex disease, and the HBM can help to understand why some of the
parents or guardians decided not to take the steps necessary to prevent this disease. I
operationalized the HBM in the current study by comparing the concepts of the model to
the beliefs or perceptions of the parent or guardian, which then leads to the decisions
made for the child. The HBM is associated with research questions 6 and 8.
Figure 2
Health Belief Model
Perceived
Susceptibility
Perceived
Severity
Perceived
Benefits
Perceived
Barriers
Cue to Action
Self-Efficacy
Note. (LaMorte, 2019)
Nature of the Study
The secondary data that were utilized in this study were archived from the
National Survey of Children’s Health (NSCH) with a cross-sectional research study
design, which was intended to identify whether there is an association between childhood
obesity and cerebral palsy, Down Syndrome, and epilepsy or seizure disorder in children
ages 0-17. The NSCH data was collected electronically or on paper via a survey (Child
and Adolescent Health Measurement Initiative, 2020). The survey was compiled by the
Health Resources and Services Administration’s Maternal and Child Health Bureau
(HRSA MCHB) to provide data on children ages 0-17 (Child and Adolescent Health
Measurement Initiative, 2020). This data included the mental, physical, and emotional
health, risk factors of both the child and parent or guardian and environmental factors
related to the child’s well-being (Child and Adolescent Health Measurement Initiative,
2020).

There are several reasons why the dataset was utilized for this research study.
The NSCH data are for public use of secondary data and are free of charge. Some data
were collected at the national level, and some were collected at the state level. The
independent and dependent variables that were utilized in this study were mainly
collected at the national level. I chose to use the national data because they provide a
broader range of data across the U.S. and because there were no state-level data available
for the selected research variables for this study.
Literature Search Strategy
I used the following databases and search engines for the literature review:
EBSCO, CINAHL, MEDLINE, Science Direct, Thoreau, and Google Scholar. Some key
search terms used when conducting research for this study were childhood obesity,
cerebral palsy, Down Syndrome, Downs Syndrome, epilepsy, seizure disorder, social
cognitive theory, health belief model, youth, obesity, overweight, children, pediatric, and
trisomy 21. The scope of the literature reviewed was between the years 2017-2022. The
majority of the articles and research found were from peer-reviewed research. There
were a few sources from textbooks, websites, and articles that either referenced Bandura
or were edited by Bandura.
Literature Review
Childhood Obesity and Health Outcomes
According to Reis et al. (2020), children living in a low-income household have a
2.31% higher chance of being obese than children living in a higher income household.
These researchers also found that there was no association between childhood obesity

and the parents’ level of education (Reis et al., 2020). In addition, children whose
parents’ income was less than $900 a month were at a higher risk of being overweight or
obese (Bazán et al., 2018). Similarly, an article indicated that children whose parents’
education level was low were at an increased risk of being overweight or obese (Bazán et
al., 2018).
Socioeconomic status, race, and age have an association with childhood obesity
(Banks et al., 2016). According to Banks et al.’s (2016) study of 12,674 participants in
grades kindergarten to eighth grade, Black males with a higher socioeconomic status had
a higher standardized body-mass index, also known as zBMI (six time points). In
contrast, the White male participants with a lower socioeconomic status had lower zBMI
scores. Therefore, the socioeconomic status, race, and sex of a child have a relationship
with childhood obesity.
As specific to children within intellectual and physical disabilities, youth who
have Down Syndrome were at a higher risk of being overweight or obese than youth
without intellectual disabilities, as concluded by Oulmane et al. (2021). Also, children
and adolescents who are newly diagnosed as epileptic and untreated have a higher risk of
being obese (Daniels et al., 2009). Epileptic obese children are considered a comorbidity,
and the relationship between the two are lack of physical activity, nutritional intake, and
the medicine that they consume due to their illness (Ladino & Téllez-Zenteno, 2019).
Meyns et al. (2016) conducted a study on the individualities of gait in children with
cerebral palsy and their effect on body weight increase. The study concluded that more
weight gain in a child is significant to the gait pattern of a child with cerebral palsy

(Meyns et al., 2016). Overall, these studies support the present research by identifying
some health concerns regarding childhood obesity.
Influential Factors of Childhood Obesity
Obesity has increased over the last four decades in the United States, with the
childhood obesity rate at 18.5% and the adult obesity rate at 39.8% (Anderson et al.,
2019). Childhood obesity is significant to discuss and study because it can lead to adult
obesity (Cohut, 2017). According to the CDC, a person’s weight status is determined by
their BMI ratio (2021). The BMI calculates a person’s weight in kilograms divided by
the height in meters (CDC, 2021). The BMI of a child is calculated based on their age, is
sex-specific, and is connected with direct body fat measurements (CDC, 2021). The
child’s percentile rate is how they are categorized. For example, an underweight child
has less than the 5th percentile, a healthy weight child has between the 5th to 85th
percentile, an overweight child has between the 85th to 95th percentile, and an obese child
is equal to or greater than the 95th percentile (CDC, 2021).
In a study conducted by Williams et al. (2018), the researchers examined the
families’ risk factors for obese children between the ages of 4-5. Some of the risk factors
examined were race and gender. In the study, 49.06% of the participants were females,
the remaining 51% were males, over 53% were White, and over 13% were Black
(Williams et al., 2018). Most of the children who had a higher prevalence rate of
childhood obesity were White males between four and five (Williams et al., 2018). In a
similar study, Assari (2018) examined the association between the parents’ income and
childhood obesity in Black and White families. The researchers used the NSCH data

from 2003-2004 to determine that the incidence rate of a family’s income and its
association with childhood obesity did not affect Black children more than White
children between the ages of 2-17 (Assari, 2018).
Lastly, Tylavsky et al. (2020) studied the environmental factors through the
Environmental Influences on Child Health Outcomes (ECHO) program and their effect
on childhood obesity in the United States. The ECHO program explores environmental
exposures to child health and development (Tylavsky et al., 2020). In the study, ECHO
was used to identify why childhood factors affect the risk of obesity (Tylavsky et al.,
2020). Several factors were utilized in this study, such as the child’s ethnicity, age, sex,
maternal demographics, and, most importantly, the child’s BMI. Children under two
who participated in the study were examined according to their high BMI scores
(Tylavsky et al., 2020). Children ages two-18 were examined according to their BMI,
based on the following categories: overweight, obese, and severe obesity (Tylavsky et al.,
2020). The researchers concluded that the child’s weight increased as their age
increased, while ethnicity varied (Tylavsky et al., 2020). Overall, there are several
environmental factors that affect a child’s weight status.
Childhood Obesity and other Countries
Childhood obesity is not only prevalent in the United States; it is also prevalent in
other countries. A study was conducted between the years 2010-2014 titled The
International Study of Childhood Obesity, Lifestyle, and the Environment (ISCOLE).
This multi-national, observational study focused on the relationship between obesity and
lifestyle factors amongst 10-year-old children residing in 12 different countries and five

major regions such as North America, Africa and Eurasia, Europe, Latin America, and
the Pacific (Katzmarzyk et al., 2019). The researchers compared the BMI and body fat of
the children and found that the Indian boys had a more significant body fat percentage
than the boys in other countries (Katzmarzyk et al., 2019). On the other hand, girls from
Kenya had a lower body fat percentage than girls in other countries (Katzmarzyk et al.,
2019). The BMI of girls and boys in Columbia was low, and the boys’ body fat
percentage was higher than the boys' in other countries (Katzmarzyk et al., 2019).
The prevalence and incidence rate of childhood obesity varies depending on many
factors, including the country or region the child resides. Overall, there are several
research studies that show the relationship between childhood obesity and cerebral palsy,
Down Syndrome, epilepsy or seizure disorder, the child’s age, race, sex, lack of physical
activity and nutritional intake, environmental factors, and the education and income level
of the parent.
Social and Emotional Factors Associated with Childhood Obesity
Obesity could cause several complications, such as social, emotional, and physical
issues (National Institute of Diabetes and Digestive and Kidney Diseases, n.d.).
Obesity is also associated with gait disorder, obstructive sleep apnea, dyslipidemia, and
hyperinsulinemia (Bertapelli et al., 2016). Children with intellectual disabilities often
also suffer from anxiety and depression (Whitney et al., 2018). Additionally, childhood
obesity can also cause many health-related issues, such as diabetes, breathing problems,
high cholesterol, high blood pressure, and joint pain (Mayo Clinic, 2020). Current
research discusses how environmental status, family beliefs, child health influences, food

intake, lack of physical activity, school environment, and other related factors contributes
to childhood obesity (Anderson et al., 2019). Many child behavioral risk factors could
increase childhood obesity. Some factors include increased time spent watching
television, playing video games, lying down or sleeping, and decreased time interacting
in physical activity (Williams et al., 2018). Some studies discuss the association between
childbirth and childhood obesity. Parental risk factors are another vital topic regarding
childhood obesity. According to Williams et al. (2018), some parental risk factors are
maternal obesity, low education, smoking, lack of nutrition knowledge, African
American race, and perceived neighborhood safety.
In the study, kindergarten-aged children suffered from childhood obesity or being
overweight because their parent was a smoker, and the child did not eat dinner as a
family (Williams et al., 2018). Children with parents who smoked had a 40% higher
chance of being overweight, while children who ate dinner with their parents had a 4%
lower chance of becoming overweight (Williams et al., 2018). Overall, according to
previous studies, the socioeconomic status of the parent and child is a risk factor for the
child being diagnosed with childhood obesity.
In a recent article, researchers determined 10 family-related factors associated
with childhood obesity. Those factors are family history of diseases, parenting styles,
parental educational status, family structure, family perception about the child’s weight,
family meal frequency, parents’ weight, occupation status, feeding practices, and
parenting styles (Notara et al., 2020). These parental factors could affect the child’s
social, emotional, and physical well-being.

Social and emotional well-being is important in a child and young adolescent’s
life (Noonan & Fairclough, 2019). Their self-perception and ability to interact with other
children are critical in their young lives. If the social and emotional well-being of a child
is not taken care of while they are young, it could spiral into more challenging
experiences in their adult lives (Noonan & Fairclough, 2019). Peer relationship problems
can lead to social and emotional anxiety and later being overweight or obese in those
young children and adolescents (Noonan & Fairclough, 2019). Children who are less
active than other children are also more likely to develop social and emotional issues,
resulting in childhood obesity (Noonan & Fiarclough, 2019).
Public Health Impact of Childhood Obesity
Childhood obesity is a public health issue raising two prime concerns: the child’s
physiological and psychological health. Psychological health affects the child’s
selfesteem and social and emotional well-being (Sanyalou et al., 2019). Children who
have emotional issues such as anxiety, mood disorders, eating disorders, and somatoform
are most likely children who have problems with their weight (Sanyalou et al., 2019).
Sanyalou et al.’s (2019) study showed that 60% of girls and 35% of boys indicated that
they have an issue with binge eating and cannot control their eating habits.
Other public health concerns for childhood obesity are type 2 diabetes, possible
diagnosis of cancer, and pulmonary disease (Sanyalou et al., 2019). These health
problems are also known as chronic inflammation diseases. One or more of the listed
inflammation diseases can lead to heart disease in the child’s adulthood. According to
Sanyalou et al.’s (2019) study, these are just a few of the reasons why it is essential for

children to learn how to control their emotions and eating habits to avoid becoming
overweight or obese.
As of 2020, $14 billion is spent on childhood weight health issues each year (State
of Childhood Obesity, 2020). One place that we could help decrease the cost is in the
education system. School districts that participate in the National School Lunch Program
(NSLP) are required to provide free, drinkable, and clean water sources in their buildings
(Kenney et al., 2019). Some educational institutions have decided to install water
dispensers in the schools to assist with this (Kenney et al., 2019). Although the
installation cost of water dispensers is between $2.74- $5.79 per child, the water jets
could reach over 29 million children, prevent 179,550 childhood obesity cases, and save
$0.31 per dollar in health care costs by 2025 (Kenney et al., 2019). Childhood obesity
can lead to many cardiovascular and detrimental health issues that must be recognized to
prevent the issue and lower the cost of this public health concern.
Prevention Efforts for Childhood Obesity
Numerous interventions have been created and implemented to prevent childhood
obesity, including family-based, community-based, and school-based. Many
interventions have been practiced in several countries, such as the United States,
Australia, and Europe (Ash et al., 2017). Ash et al. (2017) analyzed family-based
childhood obesity interventions utilizing a quantitative approach. These researchers
reviewed the many family-based interventions conducted to prevent childhood obesity
and concluded that there were gaps within the intervention designs and methodology
(Ash et al., 2017). Their study concluded that most of the interventions conducted were

mainly geared toward children ages 2-10 and less likely geared toward children ages
1117 (Ash et al., 2017). They also concluded that more family-based interventions
should be suitable for children aged 0-17 (Ash et al., 2017).
Agaronoy et al. (2018) implemented a family-based sleep promotion intervention
to help prevent childhood obesity in the United States. Agaronoy et al. (2018) concluded
that sleep promotion interventions should be used as a best practice to prevent childhood
obesity and help infants and pre-school-aged children in high-income countries. Overall,
this intervention resulted that sleep promotion can have a positive impact on a child’s
behavior, such as physical activity and a healthy diet increase which can result in
childhood obesity prevention (Agaronoy et al., 2018).
In a recent study, researchers evaluated a new family-based intervention based in
Europe that will assist in preventing childhood obesity in school-age children (Homs et
al., 2021). Homs et al. (2021) used the FItness, VAlues, and Healthy LIfestyles
(FIVALIN) project for the intervention. The FIVALIN project was put in place to help
prevent childhood obesity in children ages 8-12 and follow them through adulthood
(Homs et al., 2021). This intervention will address several factors associated with
childhood obesity, and an evaluation will be conducted after following the child and their
family for 12 months (Homs et al., 2021).
As stated above, mental health is another health issue related to childhood obesity.
Narayanan et al. (2019) conducted a school-based intervention in the United States using
health mentors to address childhood obesity. This intervention was used to strengthen
the wellness policy in Title 1 schools by implementing a behavioral change model, Team

Kid POWER! (KiPOW!) and utilizing community resources to help manage childhood
obesity (Narayanan et al., 2019). The health mentors introduced the students to the
importance of healthy eating and daily exercise or physical activity while at recess
(Narayanan et al., 2019). After four years of implementing this intervention, researchers
resulted that the KiPOW behavior change model was helpful for the students, staff, and
administrators (Narayanan et al., 2019).
Also, Gadsby et al. (2020) conducted a community-based intervention on
childhood obesity as a whole system approach. The Go-Golborne intervention conducted
in London was created to address childhood obesity by promoting healthy lifestyles
among children and families throughout the communities (Gadsby et al., 2020). The
GoGolborne campaigns and events have been successful over the years (Gadsby et al.,
2020). The community believed that the children and families were beginning to make
better healthy eating choices and participate in daily physical activity to decrease or
prevent childhood obesity (Gadsby et al., 2020). The results showed that children who
participated in the Go-Golborne intervention showed positive change and increased
knowledge of healthy foods (Gadsby et al., 2020).
Another European study focused on a combination of school-based and
familybased interventions to prevent childhood obesity. The study targeted interventions
geared toward physical activity, dietary, and sedentary behaviors among younger
children (Lambrinou et al., 2020). Some programs focused on educational sessions for
parents, and others used incentives and social marketing techniques to help prevent
childhood obesity (Lambrinou et al., 2020). The parent sessions were not as successful

as the student incentive sessions (Lambrinou et al., 2020). After researching other
childhood obesity interventions, Lambrinou et al. took those researchers’
recommendations and created an intervention titled the Feel4Diabetes Intervention to
assist with designing similar childhood obesity prevention proposals (Lambrinou et al.,
2020). Overall, there are numerous articles about the prevention of childhood obesity
and the intervention tactics researchers develop to promote prevention or decrease
childhood obesity. Schoolbased, community-based, and family-based interventions are
public health tools to help prevent or decrease childhood obesity.
Childhood Obesity and Developmental Disability
Physical disability is a long-term condition that affects a specific area or area of
an individual’s body that limits physical functioning, dexterity, and stamina (Berg, 2020).
According to the Centers for Disease Control and Prevention, cerebral palsy is the most
common childhood motor disorder in the United States (CDC, 2022). Research has
shown that children with cerebral palsy usually lack physical activity and cannot
understand balanced food intake (Bandini et al., 2015). Bandini et al. (2015) believe that
a lack of physical activity and nutritional and proportional food intake could cause
children with cerebral palsy to become overweight or obese. Haegele et al. (2019)
conducted a study focused on the weight status among children and youth with chronic
diseases such as diabetes, intellectual disabilities, hearing impairments, Down Syndrome,
epilepsy, and more based on the 2016 NSCH data. These researchers found that children
with cerebral palsy were the least prevalent group considered overweight (Haegele et al.,
2019).

There are two types of seizures: generalized onset and focal onset (Epilepsy
Foundation, 2019). A few generalized onset seizures are atonic, absence, or tonic-clonic.
(Epilepsy Foundation, 2019). The two focal onset seizures are aware seizures and
impaired awareness seizures (Epilepsy Foundation, 2019). Some causes of epilepsy are
stroke, head injury, brain tumor, Alzheimer’s disease, brain infection, genetic factors, and
malformation of an area of the brain (Epilepsy Foundation, 2019).
Haegele et al. (2019) found that being overweight was the least prevalent among
children with epilepsy. Parents of children who have epilepsy and responded to the
NCHS 2016 survey were concerned that their child’s weight was too high (Haegele et al.,
2019). According to Haegele et al. (2019), 13.9% of children with epilepsy were
overweight but fell under the least prevalent groups to be considered overweight,
according to their parents. Intellectual disabilities are significant limitations in the
adaptive behavior and intellectual functioning of a person’s mental capacity that usually
begins before 22 (American Association on Intellectual and Developmental Disabilities,
2021).
Physical disabilities are considered temporary or permanent limitations or
disabilities that affect at least one limb in a person’s body (Rutgers School of Arts and
Sciences, n.d.). CP has four types: spastic cerebral palsy, spastic diplegia, spastic
hemiplegia, and spastic quadriplegia (Rutgers School of Arts and Sciences, n.d.).
Cerebral palsy can be considered a physical and intellectual disability because it impacts
a person’s ability to move around and it causes brain abnormalities (Rutgers School of
Arts and Sciences, n.d.). Also, spastic quadriplegia CP affects facial features, limbs, and

walking capabilities and can lead to other intellectual disabilities, such as seizures
(Rutgers School of Arts and Sciences, n.d.).
Children and youth with Down Syndrome could be at a higher risk for obesity
based on behavioral or physiological factors (O’Shea et al., 2018). Some behavioral
factors are dietary and physical activity (O’Shea et al., 2018). Some physiological
factors are low mastication, low basal metabolic rate, and hypothyroidism (O’Shea et al.,
2018). O’Shea et al. (2018) used a cross-sectional approach to their study, which will
also be used in my research study. According to Haegele et al. (2019), intellectual
disabilities were one of the most prevalent reasons children were overweight. Because
Down
Syndrome was a part of the intellectual disability group in Haegele et al. (2019) study,
Down Syndrome accounted for 53.6% of the children identified as overweight. The
current study helps to fill the gap in the literature and spur further research in this area of
obesity.
Studies Using the Proposed Methodology
The method used in this proposal is observational and quantitative. There were
several studies conducted using this methodology for childhood obesity prevention. In a
most recent meta-regression quantitative study, researchers studied the relationship
between the outcome and dose (duration and how many sessions) of behavioral
intervention trials and its association with childhood obesity (Heerman et al., 2017). The
behavioral interventions were conducted in a controlled study over time between 1990
and June 2017, and the target population was children ages 2-18 years old. This study

was a secondary randomized control study that identified 258 studies and used 133
studies in their meta-regression analysis (Heerman et al., 2017). The results showed no
significant association between the study’s covariates (Heerman et al., 2017). The results
of this quantitative study did not show an association between the dose and weightrelated
outcomes. The researchers believed that more interventions should be conducted to
prevent childhood obesity and improve healthy childhood growth (Heerman et al., 2017).
Another study observed the association between community programs and
policies on a child’s dietary intake to provide suggestions on facing childhood obesity. In
previous research studies, nutrition was a huge factor in childhood obesity causes and
prevention. Ritchie et al. (2018) examined the relationship between community policies
and child nutrition in 5,138 children grades kindergarten to eighth. The conclusion of the
quantitative observational study showed that if there are additional strategies included in
the community program policies and more interventions conducted to control a child’s
limit to sugars, sweetened beverages, and energy-dense foods, it will improve children’s
diets (Ritchie et al., 2018). Ritchie et al. (2018) used secondary data from the
observational study conducted by the Healthy Communities Study (HCS) and funded by
the National Institutes of Health (NIH). This study was conducted for ten years, and
interviews collected additional data. For the data to be gathered by the minor children,
parents were asked to sign a consent form.
Furthermore, nutrition is important to childhood obesity awareness and prevention
in children ages 5-19. Carrero-González et al. (2021) conducted a study that focused on
the dietary intake habits of school-aged children who suffer from malnutrition and are

considered overweight or obese. Of the 82 children who participated in the study, 21.9%
of girls and 10.1% of boys were overweight, whereas obesity was more prevalent in boys
at 24.5% and girls at 9.7% (Carrero-González et al., 2021). The correlational study
concluded that there was a relationship between school-age children and their eating
habits and weight status (Carrero-González et al., 2021). The researchers used a
descriptive, correlational, and quantitative approach, which is the method that I am using
in my study (Carrero-González et al., 2021). Carrero-González et al. (2021) measured
the child’s BMI and created a form to capture the child’s date of birth, sex, weight,
height, and chronological age. My study focuses on the child’s race, age, sex, and weight
status. Participants were provided a questionnaire to capture their food consumption.
The data used in my study were also collected via a questionnaire by the primary
researchers. The participants were measured based on anthropometric evaluation and
classification using the nutritional diagnosis of normal weight, overweight, and obese
(Carrero-González et al., 2021). Lastly, the researchers analyzed that children ages 10-12
had overweight and obese rates of 13.89% and 74.38%, whereas children ages 12-14 had
overweight and obese rates of 12.23% and 77.21% (Carrero-González et al., 2021). Each
of these researchers used the quantitative method in their study. Still, they used other
analyses to test their hypothesis, test if there was or was not an association between the
variables, and answer their research questions.
Definitions
Body Mass Index (BMI). Calculates a person’s weight in kilograms divided by the
height in meters (Centers for Disease Control and Prevention, 2021).

Cerebral Palsy (CP). “A disability resulting from damage to the brain before,
during, or shortly after birth and outwardly manifested by muscular incoordination and
speech disturbances” (Merriam-Webster, n.d.).
Childhood Obesity. Weight over the average height and weight ratio for a child
(Childhood Obesity Foundation, 2019).
Downs Syndrome (DS). “A genetic disorder caused when abnormal cell division
results in an extra full or partial copy of chromosome 21. (trisomy-21)” (Mayo Clinic,
n.d.).
Epilepsy. is “any of various disorders marked by abnormal electrical discharges in
the brain and typically manifested by sudden, brief episodes of altered or diminished
consciousness, involuntary movements, or convulsions” (Merriam-Webster, n.d.).
Socioeconomic (SES). “Relating to or involving a combination of social and
economic factors” (Merriam-Webster, n.d.).
Assumptions
I assume that the process of collecting the data for the 2018-2019 National Survey
of Children’s Health was extensive. It is assumed that the guardians or parents of the
children understood the questions from the questionnaire and responded to surveys
honestly and truthfully. Another assumption is that all the children were between the
ages of 0-17. I assume that the process for collecting the data was rigorous, resulting in
valid data. Lastly, I assume that the original study participants received and signed an
informed consent document.

Scope and Delimitations
The data used for this research study was from the 2018-2019 National Survey of
Children’s Health. There were 59,963 completed surveys between the two years
combined, with 2018 collecting 30,530 completed surveys and 29,433 completed surveys
in 2019 (Child and Adolescent Health Measurement Initiative, 2020). The population
was weighted because the two years were combined and consisted of noninstitutionalized
children aged 0-17 nationwide and statewide (Child and Adolescent Health Measurement
Initiative, 2020). For the variables used in this research study, there were no state data
available under the 2018-2019 NSCH survey. Therefore, national data were used. When
finding the dataset for the selected variables, the indicators used were if the parent was
“ever told that child is overweight” and the “prevalence of current or lifelong conditions”
of the child.
The Social Cognitive Theory was a good model to use for the current study. The
SCT was used to promote childhood obesity prevention and help identify the outcome of
the study. Another model used in the current research study is the Health Belief Model.
The HBM was used to discuss the relationship between the variables.
The theory considered but excluded from this study was the Theory of Planned
Behavior (TPB). The TPB includes the motivational factors that consist of the reasons
and actions why individuals perform certain behaviors (Kelder et al., 2015). It does not
necessarily promote behavioral change through the several constructs of the framework
(Kelder et al., 2015). The constructs of the SCT and HBM are fundamental in facing
childhood obesity. Several other aspects of childhood obesity are essential but will not

be discussed in this study, including diabetes, heart problems, autism, attention deficit
hyperactivity disorder (ADHD), asthma, and more.
Limitations
Because this study is a secondary analysis of archived data, I am bound by the
original study’s goals, objectives, and design. I did not partake in the planning and
original data collection process. I worked on the parameters of the existing database, and
my analysis was limited to national data as state-level data were not collected in the
original study. Another limitation is that the self-reported data were collected from the
adult parents or guardians of the children. Lastly, I did not have any input on the ethical
considerations for collecting, analyzing, and storing the data. There could be bias in the
responses from the guardians, as some of them could have made false responses to one or
more of the questions regarding the variables used for this research study. The bias could
have influenced the outcomes of the study.
Significance
By studying these factors and gaining more knowledge about childhood obesity,
my study might assist with a better understanding of the factors that impact childhood
obesity. Children with cerebral palsy, Down Syndrome, and epilepsy or seizure disorder
disabilities could lead to lack of social participation, affecting their weight levels. The
lack of desire or incapability to interact socially could be detrimental to the child’s
weight. It is with the hope that the findings from this study help to promote positive
social change in children with these specific physical and intellectual disabilities and
control their weight status. Another potential social change impact of this study will be

to eventually decrease morbidity and mortality associated with obesity among youth and
children, especially those with physical disabilities.
Summary and Conclusion
Childhood obesity significantly affects a child’s physical, social, emotional,
selfesteem, and mental health (Sahoo et al., 2015). When one considers the factors of a
child who has physical or intellectual disabilities, one may not connect their disability
with their weight status. This study is a secondary analysis of archived data using the
National Children’s Health Survey database conducted between 2018 and 2019. Using
the given data, I conducted a correlational study to examine the association between
childhood obesity and cerebral palsy, childhood obesity and Down Syndrome, and
childhood obesity and epilepsy or seizure disorder. There has been very little research
conducted on some of the physical and intellectual disabilities used in this study, cerebral
palsy, Down
Syndrome, and epilepsy or seizure disorder. There is a gap in research on physical
disabilities (cerebral palsy) and their relationship to childhood obesity. There is also a
gap in research on the association between epilepsy or seizure disorder and childhood
obesity. Previous researchers recommended more research on lifestyle factors to address
the risk of childhood obesity in children with intellectual disabilities (O’Shea et al.,
2018).
This study has the potential to fill the gap of the researchers’ recommendation.
The present study filled the gap by providing data on intellectual and physical disabilities
in children ages 0-17. This study identified the relationship between the dependent and

independent variables using the NSCH 2018-2019 data. This study presented
information to better understand some physical and intellectual disability factors
associated with childhood obesity versus the other factors previously studied among
youth ages 0-17. Childhood obesity is a major public health concern that will continue to
be an ongoing research topic in further studies. This study opened research for future
studies regarding these and other physical and intellectual disabilities and their
relationship with childhood obesity or other public health issues. In section 2 of this
proposal, I will explain the methodological approach thoroughly, including a
comprehensive plan for data analysis.
Section 2: Research Design and Data Collection
Introduction
This cross-sectional study examined the association between obesity amongst
U.S. children ages 0-17 and their diagnosis of the following physical and intellectual
disabilities: cerebral palsy, Down Syndrome, and epilepsy or seizure disorder. I used a
quantitative approach. The dependent variable is childhood obesity, and the independent
variables are cerebral palsy, Down Syndrome, and epilepsy and/or seizure disorder. The
confounding variables are the socioeconomic status of the parent (education level and
income level) and the age, race, and sex of the child. Past researchers have not combined
and thoroughly studied the dependent and independent variables used in this research
study together. As such, this research study filled that gap in research. Lastly, the
variables utilized in this study were collected on a national level using data from the

NSCH’s database. No state or regional data were provided or analyzed throughout this
study.
Section 2 includes a description of the research design and rationale,
methodology, threats to validity, ethical procedures, and a summary of the information
under the subtopics. The research design states the variables used in the study, the types
of research designs used in the study, how they relate to the research questions, why the
design was selected, and why choosing a design is essential to this research study. The
methodology section explains the target population, sample strategy, inclusion and
exclusion data information, study source and access to the dataset, power analysis for
sample size, instrumentation of constructs, operationalization of the selected variables,
and the data analysis plan. The threats of validity section cover the internal and external
threats. The ethical procedures section includes details about the anonymity and security
of the dataset, along with any other ethical processes. Lastly, the summary concludes the
key points of each section.
Research Design and Rationale
The research variables are childhood obesity (dependent variable), cerebral palsy
(independent variable), Down Syndrome (independent variable), epilepsy and/or seizure
disorder (independent variable), education level of parent or guardian (confounding
variable), income level of parent or guardian (confounding variable), age of the child
(confounding variable), race of the child (confounding variable), and sex of the child
(confounding variable). The original data were collected and analyzed in numerical
format. Therefore, this study was quantitative.
A correlational study using the cross-sectional study design examines the
association between two or more variables (Seeram, 2019). The study design also
identifies the outcome and exposure of the participants (Seeram, 2019). A cross-
sectional study design will focus on both the internal and external data from the dataset
(Seeram, 2019). Cross-sectional studies are used to study a population-based survey,
calculate odds ratios (OR), and the prevalence of clinic-based studies (Seeram, 2019).
The current cross-sectional study measured the OR of the archived data. An example of
the order of operations for a cross-sectional study design is in Figure 3.
Figure 3
Cross-Sectional Study Design
Included &
Excluded
Participants
Exposure & Outcome Prevalence
& Odds
Ratio
Calculation
Because a secondary dataset was used, the cross-sectional study design was the
best study design option since there was no indication of temporality. As stated above, a
cross-sectional study design is used for population-based surveys, and the NSCH is a
population survey-designed database. Cross-sectional studies are observational study
designs that help measure the outcome and exposure of the population and their
association with the variables (Setia, 2016). A cross-sectional study design was used to
test the research questions and determine if there was an association between childhood

obesity and cerebral palsy, Down Syndrome, and epilepsy or seizure disorder. I used a
sample of the data to test my hypothesis.
A cross-sectional study is also cost-efficient, but it has a lower response rate
(Wang & Cheng, 2020). Another advantage of this type of study is that it is
timeefficient, as the primary researchers do not follow the participants over time
(Seeram, 2019; Wang & Cheng, 2020). Overall, the design choice was vital when
conducting a research study like this because it allowed me to understand their study,
interpret the data’s outcome and exposure, and answer the research questions. It also
allowed me to measure the association between the variables using the dataset.
Methodology
Data Sampling
This section describes the methodology used for this quantitative study. This
section provides a brief synopsis of the original study’s data collection. The NSCH’s
2018-2019 survey’s original data collection used a random sampling strategy to identify
households with children by using a screener questionnaire. The questionnaire was
mailed to the homes, and an adult who is the caretaker of the children in the household or
the person who knew most about the children’s health completed the survey. The adult
was then given the option to complete the short screening via electronic or paper form.
From the completed surveys, if there were more than four children in the household, the
screeners asked additional questions about the four youngest children (Child and
Adolescent Health Measurement Initiative, 2019). Once that information was collected,
a child-level topical questionnaire was administered. The topical questionnaire was

divided into three age groups: 0-5, 6-11, and 12-17. The adult who completed the survey
for the child had to be 18 years or older, and preferably the parent of the child whose
health information was being shared. Excluded participants were those 18 and above (U.
S. Census Bureau, 2020).
Original Data Sampling
The National Center for Health Statistics (NCHS) is a branch of the Centers for
Disease Control and Prevention (Data Resource Center for Child & Adolescent Health,
n.d.). They help conduct and collect the data from the surveys (Data Resource Center for
Child & Adolescent Health, n.d.). Since the NSCH began providing data on mental
health, health care needs, and well-being of children ages 0-17 in the United States in
2003, the data has been used by multiple researchers (Data Resource Center for Child &
Adolescent Health, n.d.). The NSCH survey was initially only conducted in 2003, 2007,
and 2011/2012, but four years later, in 2016, it began to be conducted every year (Data
Resource Center for Child & Adolescent Health, n.d.). Because the CDC and the Census
Bureau are involved, the NSCH is a reliable source for data collection and research. The
Data Resource Center for Child and Adolescent Health is responsible for cleaning and
labeling the data for public exploration and use (Child and Adolescent Health
Measurement Initiative, 2020).
Several instruments were used for the original data collection: web questionnaire,
email questionnaire, paper questionnaire, telephone questionnaire, and Spanish language
translations (U. S. Census Bureau, 2020). The U.S. Census Bureau conducted the
surveys on behalf of the HRSA MCHB (U.S. Census Bureau, 2019). Once the data from
the current study was cleaned, the target population sample size was determined.

Original Study Data and Target Population
In the 2018 original dataset, there were initially 176,000 households selected, but
only 71,000 surveys were completed (U.S. Census Bureau, 2019). A follow-up survey
was generated, and only 38,140 surveys were completed (U.S. Census Bureau, 2019). Of
the 38,140 completed follow-up surveys, 30,530 households completed the interviews,
which was concluded in the dataset of 30,530 participating households (U.S. Census
Bureau, 2019). Table 1 illustrates the 2018 unweighted data of the original study
population in the order of operation.
In the 2019 original dataset, there were initially 184,000 households selected, but
only 68,500 surveys were completed (U.S. Census Bureau, 2020). Of the completed
surveys, 35,760 were eligible for the follow-up questionnaire (U.S. Census Bureau,
2020). Of the eligible households, only 29,433 completed the interviews, which gave the
final number of surveys that could be used for the dataset (U.S. Census Bureau, 2020).
Table 2 illustrates the 2019 unweighted data of the original study population in the order
of operation.
Table 1
2018 Unweighted Primary Data in Sequential Order
Data Listed in Sequential Order Unweighted Numbers
Completed Screeners/Surveys 71,000
Screeners with Children 38,140
Completed Screeners with Children 30,530
Total Cases 176,000
Table 2
2019 Unweighted Primary Data in Sequential Order

Data Listed in Sequential Order Unweighted Numbers
Completed Screeners/Surveys 68,500
Screeners with Children 36,196
Completed Screeners with Children 29,433
Total Cases 180,000
The target population of the original data collected was households with children
ages 0-17. The total estimated population size of the NSCH 2018-2019 dataset was
356,000 cases. Of the estimated possible cases, only 286,000 were occupied households.
There were 161,000 estimated responses from the targeted audience with children
residing in the home. After identifying the houses that had children, the data collectors
checked for completed screeners, which were a total of 139,000 cases. Once that data
was collected, the number of completed screeners that included children were identified
at 74,336 cases. A topical survey was sent out to 74,336 participants, and 59,963 of the
topical surveys were completed. A randomized sample was conducted for this dataset,
and one child from each household was included in the data. All screeners and surveys
were completed by an adult in the home that knew the child best.
Access to the Dataset
The NSCH database is reputable because it has been used in many successful
studies. Another reason that the NSCH data is reputable is because of its sponsors. The
sponsors are as follows: The Health Resources and Services Administration’s Maternal
and Child Health Bureau (HRSA MCHB), the United States (US) Census Bureau, US
Department of Health and Human Services, CDC, National Center on Birth Defects and
Developmental Disabilities (NCBDDD), United States Department of Agriculture
(USDA), Food and Nutrition Service, and the United States Environmental Protection

Agency (EPA) (2018 only) (Child and Adolescent Health Measurement Initiative, 2020).
Each of these organizations is respected and heavily utilized in most health-related
research. The NSCH database has a track record of collecting data. The institution has
an excellent reputation, and the data is viable and collected scientifically.
The Data Resource Center for Child and Adolescent Health (DRC) has a website
that provides the procedure for gaining access to the 2018-2019 NSCH survey dataset.
The data query provides interactive access to the data at the national and state levels. The
data query also breaks down the topics and subtopics of the children’s health and
demographics. The questionnaire collected all the necessary information (Child and
Adolescent Health Measurement Initiative, 2020).
Because the NSCH dataset is for public use, permission to receive access to the
needed codebook data was easy to obtain. The codebook was available on the Data
Resource Center for Child and Adolescent Health website under the CAHMI section
(Child and Adolescent Health Measurement Initiative, 2020). The Child and Adolescent
Health Measurement Initiative (CAHMI) leaders ask that all who use the data keep them
abreast of the publications and presentations. This data set represented the best source
for my study because it provided information regarding my dependent and independent
variables. Professionals and reliable organizations collected the data, and it is available
for secondary use, which was important for the study.
Present Study Data Sampling and Target Population
I used all available cases in the dataset for this study (N = 59,963). The target
population for the present study included children ages 0-17 who had been told they were

overweight and children with cerebral palsy, Down Syndrome, and epilepsy or seizure
disorder. In 2018, there were 30,402 children between the ages of 0-17 whose guardians
answered questions regarding cerebral palsy. There were 30,445 completed surveys with
responses to Down Syndrome, and 30,427 completed surveys that were responded to
regarding epilepsy or seizure disorder. In 2019, there were 29,323 children between the
ages of 0-17 whose guardians answered questions regarding cerebral palsy. There were
29,373 completed surveys with responses to Down Syndrome, and 29,342 completed
surveys that responded to epilepsy or seizure disorder. The sample size for 2018-2019
estimated totals are 59,725 for cerebral palsy, 59,818 for Down Syndrome, and 59,769
for epilepsy or seizure disorder. Table 3 illustrates the present total study population by
the independent variables and year(s).
Inclusion and Exclusion
The inclusion of cases in the current study were children ages 0-17 whose parent
or guardian responded to the following questions: ever being told by a healthcare
professional that their child was overweight (indicator 1.4b) if the child currently has
cerebral palsy (indicator 1.9a), ever told by a healthcare professional that their child has
Down Syndrome (indicator 1.9b), and if the child currently has epilepsy or seizure
disorder (indicator 1.9c). There were 59,719 responses to whether they were or were not
ever told that their child was overweight. There were 59,707 parents or guardians that
answered either yes or no on whether their child currently has cerebral palsy. There were
59,818 responses to whether their child currently has or was never told their child has

Down Syndrome. There were 59,511 responses to whether their child has or does not
have epilepsy or seizure disorder.
The current study focused only on the children who were told they were
overweight and children who have cerebral palsy, Down Syndrome, and epilepsy or
seizure disorder. Children were excluded based on the criteria of the research questions
and the purpose of the study. They were also excluded if there were responses based on
ever told but do not currently have the condition. The final study sample was identified
after the data was cleaned and prepared for analysis.
Table 3
Sample Size for Years (Individually and Combined) by Variables
Independent Variable 2018 Sample Size 2019 Sample Size 2018-2019 Sample Size
Cerebral Palsy 30,402 29,323 59,725
Down Syndrome 30,445 29,373 59,818
Epilepsy/Seizure Disorder 30,427 29,342 59,769
Totals 91,274 88,038 179,312
Note: Sample sizes are based on the total U.S. population and households; data includes “has,” “does not
have,” and “never told child has condition.”
To break down the current study target population, in the NSCH 2018-2019
combined data, there is a sample count of 4,076 children who were told they were
overweight. There is a sample count of 174 children who currently have cerebral palsy.
There is a sample size of 104 responses stating they were told their child has Down
Syndrome. Lastly, there is a sample size of 377 children who were told they currently
have epilepsy or seizure disorder.

Sample Size
I used the SPSS system to analyze the uncleaned data. I sampled all available
cases in the dataset. G*power was used to calculate the sample size and power analysis
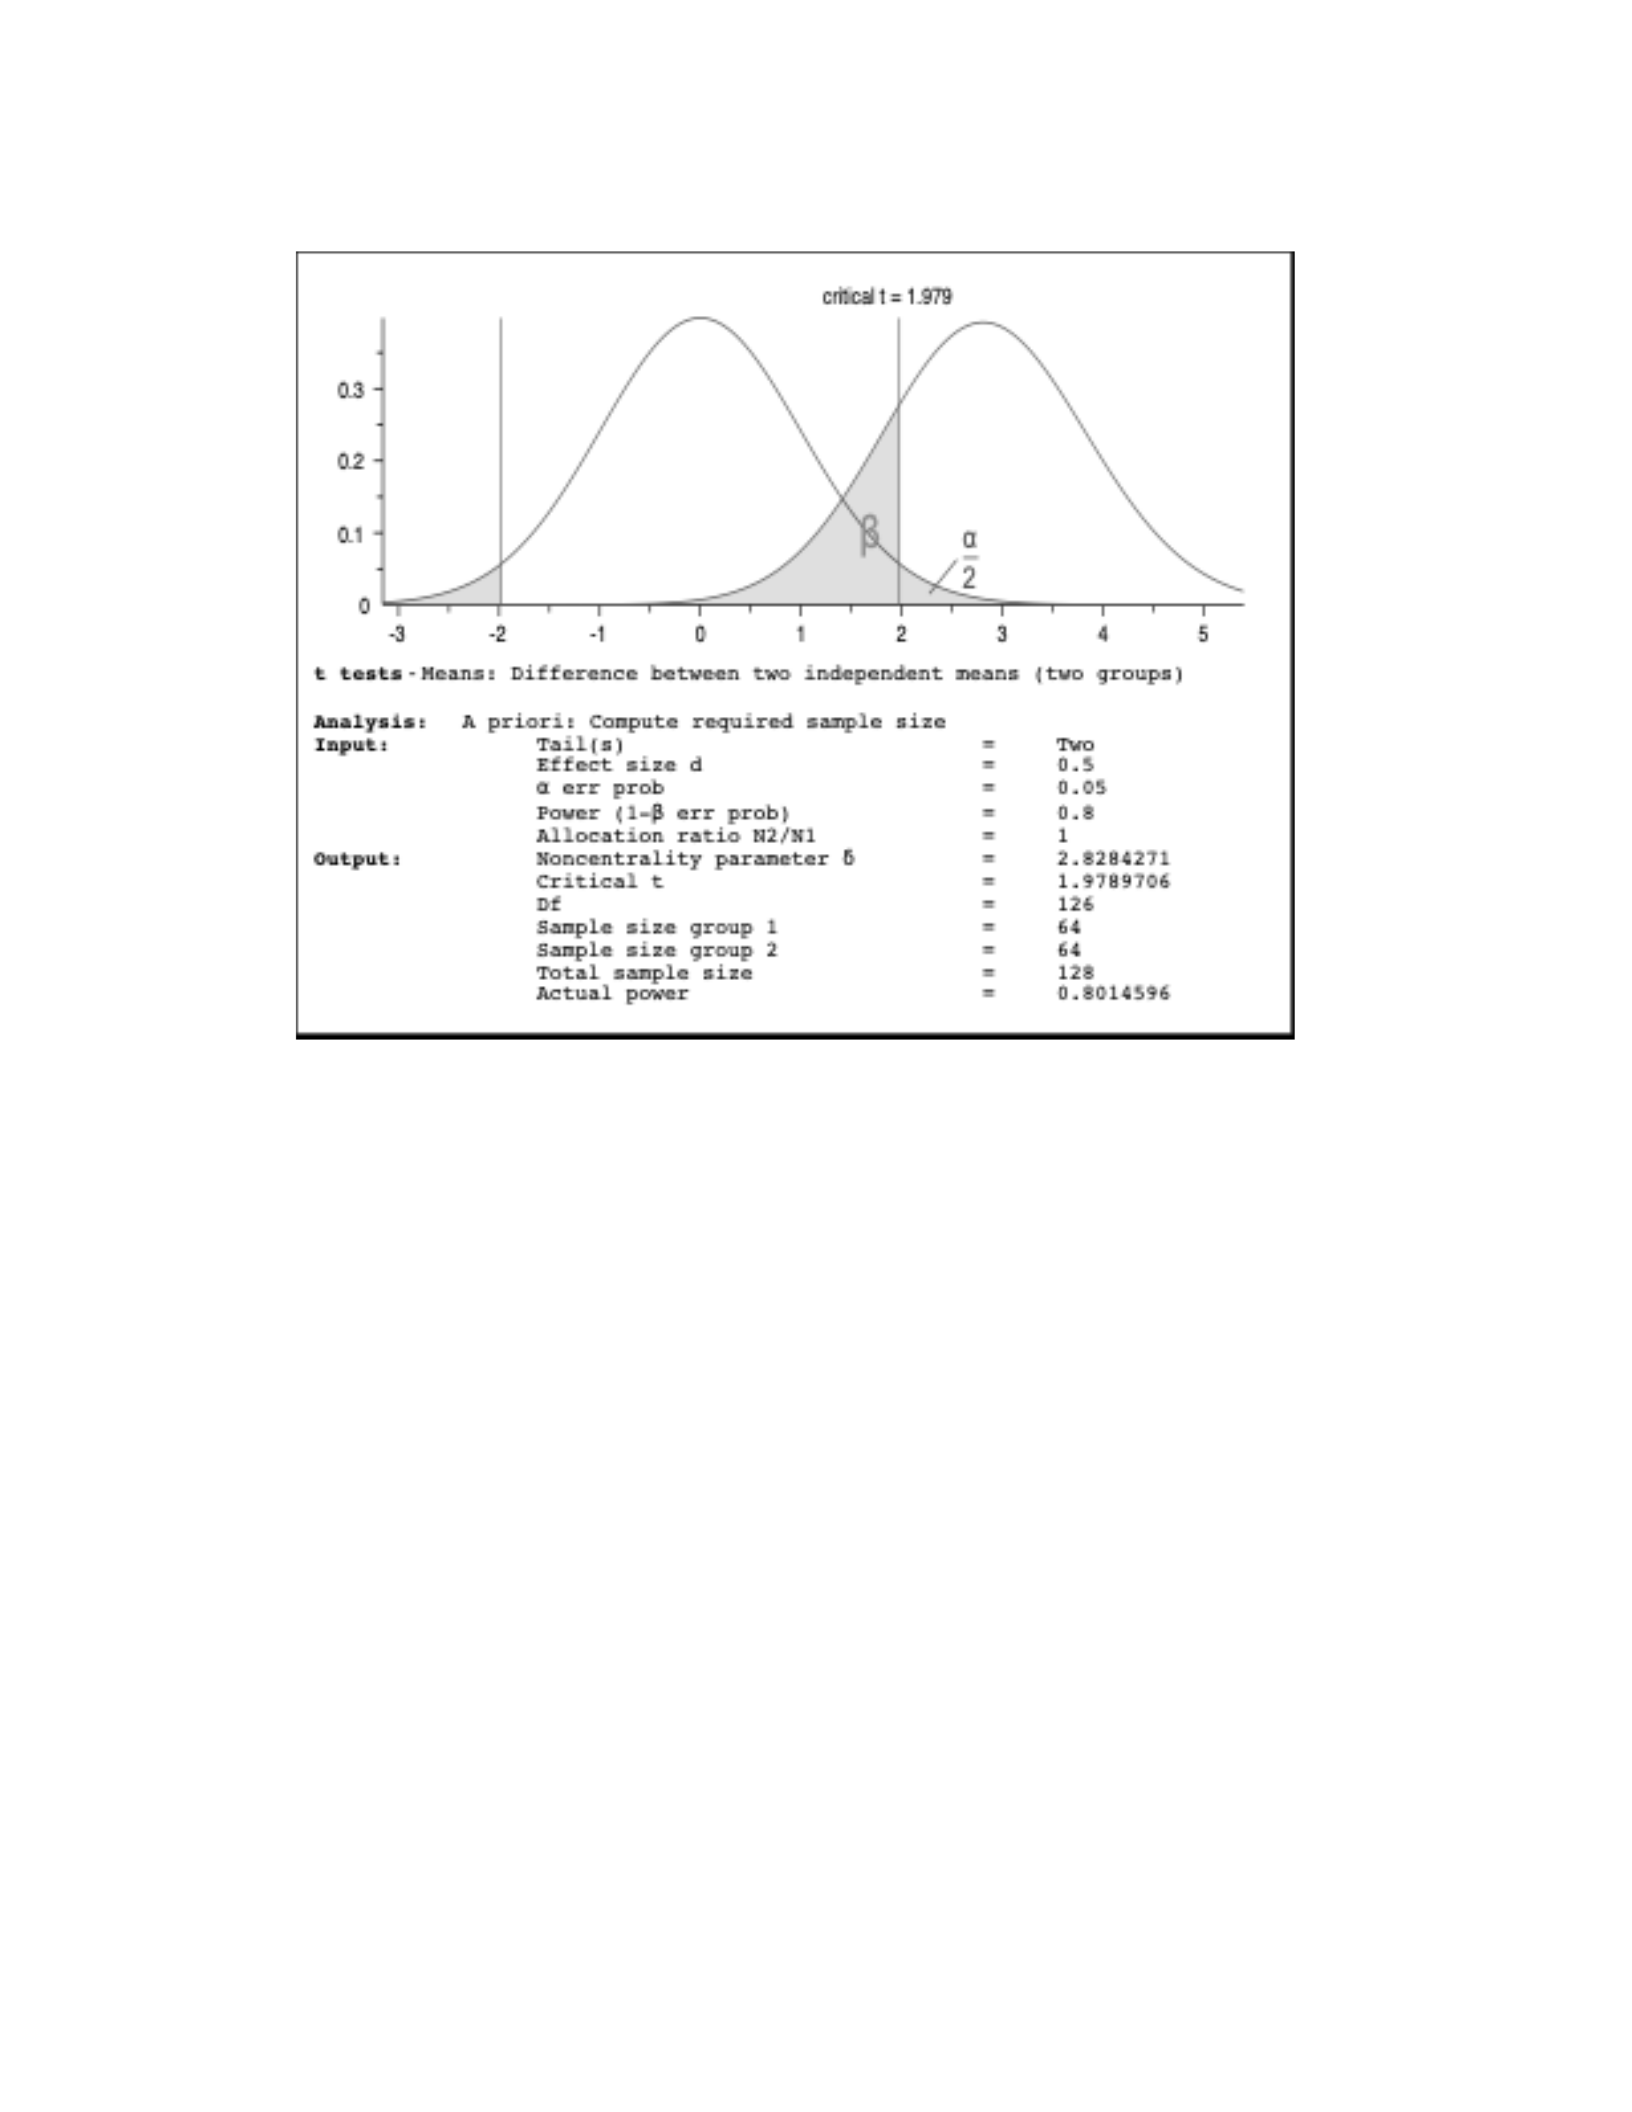
(Kang, 2021). When calculating the sample size using G*power, the following was used:
t-test (test family), means difference between two independent means, two groups
(statistical test), and a priori compute required sample size given α, power, and effect size
(type of power analysis). The input parameters consisted of two tails, effect size d at 0.5
(medium), α at 0.05, power at .80, and allocation ratio N2/N1 at 1. The outcome
parameters were computed to the following: Df at 126, sample size group 1 at 64, sample
size group 2 at 64, total sample size at 128, and actual power at 0.8014596. Therefore,
the sample size for the independent variables must be around 128 for the power to be
80%. Figure 4 illustrates the results. Given the original dataset’s large sample size and
the G*power test results comparing the means of two independent variables, I was
confident that I would have a medium study sample after data preparation. However,
after the data were cleaned, my study resulted in a small study sample size.
Figure 4
G*power Analysis
Post Hoc Power Analysis
The post hoc analysis is conducted after I have the sample size for the current
study (Kang, 2021). I conducted a post hoc power analysis to determine the actual power
of the study. Using the sample size (N), effect size, and the given α, the power level can
be determined (Kang, 2021). The post hoc formula is the alpha level (α) divided by the
number of tests. Post hoc analysis is known as a “statistical power 1-β and is figured as a
function of significance level α, sample size, and population effect size” (Faul et al.,
2009). After determination of the sample size, I reached a medium effect size (OR=3.5),
an alpha level of .05, and a power of .80 to produce reliable estimates.
Data Analysis Plan

Data Preparation
There are six steps to data preparation: access the data, ingest the data, cleanse the
data, format the data, combine the data, and analyze the data (Bhanot, 2021). I accessed
the data from the NSCH website. I also accessed the data by reviewing other research
studies that have utilized or collected data on childhood obesity, cerebral palsy, Down
Syndrome, and epilepsy or seizure disorder. Once I gained access to the necessary data, I
ingested the data by using software to review the data. Although the latest package is the
28th version, the software used to analyze the data was the Statistical Package for the
Social Sciences (SPSS) 27th version (IBM, n.d.). I only used the data necessary to answer
my research questions.
Recoding was another helpful tool for breaking down the categories into smaller
categories (Babbie, 2006). Recoding is complicated because several steps should be
taken to recode the data (Babbie, 2006). If there is a random sample, the validity will be
high due to there not being a specific population being targeted. Random sampling can
limit the data and makes room for mistakes and additional tests. The NSCH stated that
the DRC takes the results, codes them, and makes the data available to the public, making
the original data collection rigorous (2022).
Data Cleaning
I used the SPSS software to clean and screen the needed data and identify the
missing data and cases during the data cleaning and screening process. I checked for
spelling, errors, blank cells, duplicated cells, spacing, formatting, missing cells, and
number or word conversions (Bhanot, 2021). There were some missing data that were

excluded from the study. The missing data and outliers depended on the values of the
data. Data cleaning assisted with re-labeled cases. There were no duplicated cells within
the data. Therefore, I did not highlight the cells to indicate the duplicated values. Each
variable was cleaned so that I could identify the necessary data from the unnecessary
data. Once I cleaned the data, I formatted the data. There were no duplicated dates,
inconsistent abbreviations, or unnecessary data. After the data formation was completed,
I checked for missing data and identified the missing data and cases (Bhanot, 2021).
After those cases were identified as missing, I excluded the cases from the study (Bhanot,
2021). By using the preparation steps named above, I was able to analyze the data and
perform tests with the cleaned dataset. The data-cleaning process was a key instrument
for my research study.
Operationalization of Dependent and Independent Variables
The dependent variable, childhood obesity, was measured using the question,
“Has a doctor or other health care provider ever told you that this child is overweight?”
and solely on the memory of the parent or guardian. The weight status of the child was
not confirmed by checking the child’s weight or BMI for age (Child and Adolescent
Health Measurement Initiative, 2021). In the current study, I recoded the dependent
variable as 0=no and 1=yes. The independent variable cerebral palsy, was based on
parent recollection and measured using the question, “Does this child currently have
cerebral palsy?”; therefore, it was defined as self-reported guardian responses. I identified
the responses for cerebral palsy as 1= does not have the condition, 2= ever told but do not
currently have the condition, and 3= currently have the condition. The independent

variable Down Syndrome was measured using the following question, “Does this child
have Down Syndrome?” and it was also based on parent recollection; therefore, it was
defined as self-reported responses. I categorized the responses for Down Syndrome as 1=
never had condition and 2= has condition. The independent variable, epilepsy or seizure
disorder, was measured using the question, “Does this child currently have epilepsy or a
seizure disorder?” and was based on the knowledge of the parent: therefore, it was
defined as self-reported responses. I identified the responses for epilepsy or seizure
disorder as 1= does not have the condition, 2= ever told but do not currently have the
condition, and 3= currently have the condition.
Operationalization of Confounding Variables
The confounding variables were the sex, age, and race of the child as well as the
education and income level of the parent. Sex was measured using the question “What is
the child’s sex?” and was based on the parent’s recollection. The variable was identified
as 1= male and 2= female. Age was measured using the question “How old is this child?”
with a note explaining to the parent that if the child is less than 1 month, round their age
up to 1 month. The responses were given based on the parent’s recollections. I
categorized the responses to the age as 1= 0-5 years, 2= 6-11 years, and 3= 12-17 years.
Race was measured using the question “What is the child’s race?” with a pro question
inquiring whether the child was of Hispanic, Latino, or Spanish origin. The responses
were based on the knowledge of the guardian. I identified the responses for race of the
child as 1= Hispanic, 2= White, Non-Hispanic, 3= Black, Non-Hispanic, and 4= Other
Multiracial, Non-Hispanic. The education level of the parent or guardian was measured

using the question “What is the highest grade or level of school you have completed?”
and was based on the parent's knowledge. I categorized the parent’s education level as 1=
less than high school, 2= high school or GED, 3= some college or technical school, and
4= college degree or higher. The final confounding variable, the income level of the
parent, was measured by asking the parent what their income for the previous year was.
The responses were based solely on the guardian’s recollection. Based on the federal
poverty level (FPL) of 2018 and 2019, the responses were categorized as 1= 0-99% FPL,
2= 100-199% FPL, 3= 200-399% FPL, and 4= 400% FPL or greater. Table 37 in
Appendix T shows a visual of the breakdown of the operationalization for the dependent,
independent, and confounding variables.
Research Questions
According to the NSCH 2018-2019 codebook, the child’s weight status (DV) was
measured by an individual item based on the parents’ knowledge (Child and Adolescent
Health Measurement Initiative (CAHMI) (2021). The data on the dependent variable was
collected based on whether the parent or guardian was ever told by a doctor or health care
professional that their child was overweight. The codebook also indicated that the child’s
overweight status is not verified by the child’s weight or BMI per the child’s age. The
parent either responded yes or no.
According to the NSCH 2018-2019 codebook, the independent variables cerebral
palsy, Down Syndrome, and epilepsy or seizure disorder were measured and originated
from responses by the parent or guardian to the health condition question regarding 1 or
more current or lifelong health conditions (Child and Adolescent Health Measurement

Initiative (CAHMI) (2021). The survey question further asked if the parent or guardian
was ever told by a healthcare professional or educator that the child has the condition or
whether the child currently has the condition (Child and Adolescent Health Measurement
Initiative (CAHMI) (2021). Additional options were, the child does not have condition,
parent was told, but the child does not currently have condition and the child currently
has condition (Child and Adolescent Health Measurement Initiative (CAHMI) (2021).
Each independent variable was compared with the dependent variable to see if there was
an association between each independent variable and the dependent variable. For the
current study, the variables were measured using the SPSS 27th version. The eleven
research questions and their null hypotheses (H0) and alternative hypotheses (H1) are as
follows:
RQ1: Is there an association between childhood obesity and cerebral palsy?
H01: There is no association between childhood obesity and cerebral palsy.
H11: There is an association between childhood obesity and cerebral palsy.
RQ2: Is there an association between childhood obesity and cerebral palsy when
controlling for socioeconomic status of parent, education level of parent, income level of
parent or guardian, and the age, race, and sex of child?
H02: There is no association between childhood obesity and cerebral palsy when
controlling for socioeconomic status of parent, education level of parent, income level of
parent or guardian, and the age, race, and sex of child.

H12: There is an association between childhood obesity and cerebral palsy when
controlling for socioeconomic status of parent, education level of parent, income level of
parent or guardian, and the age, race, and sex of child.
RQ3: Is there an association between childhood obesity and Down Syndrome?
H03: There is no association between childhood obesity and Down Syndrome.
H13: There is an association between childhood obesity and Down Syndrome.
RQ4: Is there an association between childhood obesity and Down Syndrome
when controlling for socioeconomic status of parent, education level of parent, income
level of parent or guardian, and the age, race, and sex of child?
H04: There is no association between childhood obesity and Down Syndrome
when controlling for socioeconomic status of parent, education level of parent, income
level of parent or guardian, and the age, race, and sex of child.
H14: There is an association between childhood obesity and Down Syndrome
when controlling for socioeconomic status of parent, education level of parent, income
level of parent or guardian, and the age, race, and sex of child.
RQ5: Is there an association between childhood obesity and epilepsy or seizure
disorder?
H05: There is no association between childhood obesity and epilepsy or seizure
disorder.
H15: There is an association between childhood obesity and epilepsy or seizure
disorder.

RQ6: Is there an association between childhood obesity and epilepsy or seizure
disorder when controlling for socioeconomic status of parent, education level of parent,
income level of parent or guardian, and the age, race, and sex of child?
H06: There is no association between childhood obesity and epilepsy or seizure
disorder when controlling for socioeconomic status of parent, education level of parent,
income level of parent or guardian and the age, race, and sex of child.
H16: There is an association between childhood obesity and epilepsy or seizure
disorder when controlling for socioeconomic status of parent, education level of parent,
income level of parent or guardian, and the age, race, and sex of child.
RQ7: Does the education level of the parent or guardian have a moderation effect
on the association between childhood obesity and cerebral palsy, Down Syndrome, and
epilepsy or seizure disorder?
H07: The education level of the parent or guardian does not have a moderation
effect on the association between childhood obesity and cerebral palsy, Down Syndrome,
and epilepsy or seizure disorder?
H17: The education level of the parent or guardian does have a moderation effect
on the association between childhood obesity and cerebral palsy, Down Syndrome, and
epilepsy or seizure disorder?
RQ8: Does the income level of the parent or guardian have a moderation effect on
the association between childhood obesity and cerebral palsy, Down Syndrome, and
epilepsy or seizure disorder?

H08: The income level of the parent or guardian does not have a moderation
effect on the association between childhood obesity and cerebral palsy, Down Syndrome,
and epilepsy or seizure disorder?
H18: The income level of the parent or guardian does have a moderation effect on
the association between childhood obesity and cerebral palsy, Down Syndrome, and
epilepsy or seizure disorder?
RQ9: Does the age of the child have a moderation effect on the association
between childhood obesity and cerebral palsy, Down Syndrome, and epilepsy or seizure
disorder?
H09: The age of the child does not have a moderation effect on the association
between childhood obesity and cerebral palsy, Down Syndrome, and epilepsy or seizure
disorder.
H19: The age of the child has a moderation effect on the association between
childhood obesity and cerebral palsy, Down Syndrome, and epilepsy or seizure disorder?
RQ10: Does the race of the child have a moderation effect on the association
between childhood obesity and cerebral palsy, Down Syndrome, and epilepsy or seizure
disorder?
H010: The race of the child does not have a moderation effect on the association
between childhood obesity and cerebral palsy, Down Syndrome, and epilepsy or seizure
disorder?
H110: The race of the child has a moderation effect on the association between
childhood obesity and cerebral palsy, Down Syndrome, and epilepsy or seizure disorder?

RQ11: Does the sex of the child have a moderation effect on the association
between childhood obesity and cerebral palsy, Down Syndrome, and epilepsy or seizure
disorder?
H011: The sex of the child does not have a moderation effect on the association
between childhood obesity and cerebral palsy, Down Syndrome, and epilepsy or seizure
disorder?
H111: The sex of the child has a moderation effect on the association between
childhood obesity and cerebral palsy, Down Syndrome, and epilepsy or seizure disorder?
To answer each research question, I developed an analysis plan and had a clear
definition of the terminology used for the study (construct validity). When constructing
validity, I showed how well each test measures the perception it was intended to assess
(Bhandari, 2022). I needed to understand the different terms used to identify the
categories and levels of the data (Simpson, 2015). Some terms were variables, values,
nominal variable, dichotomous variable, ordinal variable, categorical variables, interval
variable, ratio, continuous variable, dependent variable, and independent variable
(Simpson, 2015). Other terms were descriptive statistics and inferential descriptive
statistics.
Descriptive Statistics
Descriptive statistics were used to describe the most common categories within
my study (Simpson, 2015). I used descriptive statistics to describe the selected study
population characteristics, such as the race of the child, age of the child, sex of the child,
the income of the parent, and the educational level of the parent. Descriptive statistics

provided the averages of the data. Descriptive statistics also include measures of central
tendency, variability, and distribution to measure the data. The central tendency
measures the dataset’s mean, median, and mode (Guetterman, 2019). Variability
measures the standard deviation, range, kurtosis, skewness, and minimum and maximum
values of the dataset, and distribution measures the variations in the outcome of the data
(Guetterman, 2019). I used the Chi-square test to analyze the categorical data. The
Chisquare test helped to determine the correlation of the data and provided me with a
pvalue. The p-value then told me the significance of my test results and gave me more
insight into my study population (Glen, 2022). Mock examples of descriptive statistics
illustrations are in Appendices C-G. Table 17 shows the age distribution by diagnosis.
Table 18 shows the race distribution by diagnosis. Table 19 shows the sex distribution by
diagnosis. Table 20 shows the relationship between the prevalence of the DV and the
parent’s income. Table 21 indicates the relationship between the prevalence of the DV
and the parent’s education level.
Inferential Data Analysis
Logistic Regression
Logistic regression was the best regression analysis to use for my study because
the outcome, childhood obesity (DV), is dichotomous. The outcome or dependent
variable was re-coded to 0 = not obese; 1 = obese. Logistic regression was used to
describe how variables were associated with the outcome and estimate the outcome of the
value of the variables (Hanson, 2022). Logistic regression also described the cases’
absolute and relative risk (Hanson, 2022). Lastly, logistic regression explained the

relationship between the binary DV and each IV. Since the original data methodology
stated that they used follow-up data, this study used logistic regression.
Assumptions of Logistic Regression
All variables in this study are categorical. The DV (childhood obesity) is a
dichotomous categorical variable. The categories for childhood obesity are ‘yes” or “no”
and will be coded as 0= no and 1=yes. The IVs (cerebral palsy, Down Syndrome, and
epilepsy or seizure disorder) are also categorical variables. Thus, logistic regression was
used to examine the bivariate association between the DV and IV’s. To examine whether
the bivariate association remains even after controlling for confounding, multivariate
logistic regression was used. Childhood obesity is the outcome variable, and the outcome
variable is mutually exclusive. To test this, I examined the probability of the mutually
exclusive variables. Inferential data analysis assessed the relationships between
variables. By utilizing one or more tests stated above, I tested the hypothesis of each
research question. Below in Table 4 is a data analysis matrix example of my research
questions. For each of the research questions listed, the type of analysis was both
descriptive and inferential, and the statistics used for logistic, regression, and Chi-square.
Table 4
Research Questions Data Analysis Matrix
Research Questions Level of Analysis (Bivariate or
Multivariate)
RQ1: Is there an association between childhood obesity and
cerebral palsy? Bivariate
RQ2: Is there an association between childhood obesity and
cerebral palsy when controlling for socioeconomic status of
parent, education level of parent, income level of parent or
guardian, and the age and race of the child?
Multivariate
RQ3: Is there an association between childhood obesity and Down Bivariate

Syndrome?
RQ4: Is there an association between childhood obesity and
Down Syndrome when controlling for socioeconomic status
of parent, education level of parent, income level of parent
or guardian, and the age and race of child?
Multivariate
RQ5: Is there an association between childhood obesity and
epilepsy or seizure disorder? Bivariate
RQ6: Is there an association between childhood obesity and
epilepsy or seizure disorder when controlling for
socioeconomic status of parent, education level of parent,
income level of parent or guardian, and the age and race of
child?
Multivariate
RQ7: Does the education level of the parent or guardian have
a moderation effect on the association between childhood
obesity and cerebral palsy, Down Syndrome, and epilepsy or
seizure disorder?
Multivariate
RQ8: Does the income level of the parent or guardian have a
moderation effect on the association between childhood
obesity and cerebral palsy, Down Syndrome, and epilepsy
or seizure disorder?
Multivariate
RQ9: Does the age of the age child have a moderation effect
on the association between childhood obesity and cerebral
palsy, Down Syndrome, and epilepsy or seizure disorder? Multivariate
RQ10: Does the race of the child have a moderation effect on
the association between childhood obesity and cerebral
palsy, Down Syndrome, and epilepsy or seizure disorder?
Multivariate
RQ11: Does the sex of the child have a moderation effect
on the association between childhood obesity and cerebral
palsy, Down Syndrome, and epilepsy or seizure disorder?
Multivariate
Inferential statistics are used to measure the data using the following tests: the
Chi-square test, t-test, ANOVA test, ANCOVA test, correlation, and bivariate &
multivariate regression tests (Guetterman, 2019). The bivariate and multivariate logistic
regression tests identified the association between childhood obesity and cerebral palsy,
Down Syndrome, and epilepsy or seizure disorder.
Threats to Validity
The original dataset includes merged cells based on the number of cases (U.S.
Census Bureau, 2020). For instance, individual cells that housed less than 30 cases were

combined with a neighboring cell (U.S. Census Bureau, 2020). Combining the cells
could have caused a threat to validity. This research study examined a population of
African Americans, White Americans, Hispanics, and non-Hispanics, but there is a
different ethnic population, Asian non-Hispanics, that could have been a part of the
combined cells mentioned above.
Ethical Procedures
As stated in the previous section, I am bound by how NSCH collected the data,
and I assume the ethical procedures conducted were handled effectively and efficiently. I
did not receive any raw data or analyzed data until I received IRB approval from Walden
University. I did not accept or analyze any data that contained personal identifiers. I will
store the data on a computer where only I have access to the password and share the
information with my committee chair and members. Data and analysis will be kept for a
minimum of 5 years.
Summary
The problem that was addressed in this research study is the paucity of research
on the association between childhood obesity and cerebral palsy, Down Syndrome, and
epilepsy or seizure disorder. This quantitative study aims to examine the relationship
between childhood obesity and physical and intellectual disabilities among United States
children ages 0-17. I used the NSCH dataset for this study. My proposed data analysis
plan included bivariate and multivariate logistic regression and descriptive statistics to
analyze the data and test the hypotheses. I prepared the data for analysis, including

addressing missing data and outliers. I also conducted a post hoc power analysis to
ascertain the final study power.
I assume that the original data collection was completed using valid and rigorous
scientific methods. This study will potentially promote positive social change by
increasing childhood obesity awareness and decreasing morbidity and mortality
associated with obesity among youth and children. In section 3, I presented the results of
the data analysis.
Section 3: Presentation of the Results and Findings
Introduction
The purpose of this quantitative study was to examine the association between
childhood obesity and cerebral palsy, Down Syndrome, and epilepsy or seizure disorder
while controlling for the child’s age, race, and sex, as well as the income and education
level of the guardian. This study also addressed the number of overweight, intellectually,
and physically disabled children included in the National Survey of Children’s Health
2018-2019 dataset. This study also examined the relationship between the dependent
variable and independent variables, controlling for the confounding variables. I used
secondary data to analyze this study. The research questions and null and alternative
hypotheses are as follows.
RQ1: Is there an association between childhood obesity and cerebral palsy?
H01: There is no association between childhood obesity and cerebral palsy.
H11: There is an association between childhood obesity and cerebral palsy.

RQ2: Is there an association between childhood obesity and cerebral palsy when
controlling for socioeconomic status of parent, education level of parent, income level of
parent or guardian, and the age, race, and sex of child?
H02: There is no association between childhood obesity and cerebral palsy when
controlling for socioeconomic status of parent, education level of parent, income level of
parent or guardian, and the age, race, and sex of child.
H12: There is an association between childhood obesity and cerebral palsy when
controlling for socioeconomic status of parent, education level of parent, income level of
parent or guardian, and the age, race, and sex of child.
RQ3: Is there an association between childhood obesity and Down Syndrome?
H03: There is no association between childhood obesity and Down Syndrome.
H13: There is an association between childhood obesity and Down Syndrome.
RQ4: Is there an association between childhood obesity and Down Syndrome
when controlling for socioeconomic status of parent, education level of parent, income
level of parent or guardian, and the age, race, and sex of child?
H04: There is no association between childhood obesity and Down Syndrome
when controlling for socioeconomic status of parent, education level of parent, income
level of parent or guardian, and the age, race, and sex of child.
H14: There is an association between childhood obesity and Down Syndrome
when controlling for socioeconomic status of parent, education level of parent, income
level of parent or guardian, and the age, race, and sex of child.

RQ5: Is there an association between childhood obesity and epilepsy or seizure
disorder?
H05: There is no association between childhood obesity and epilepsy or seizure
disorder.
H15: There is an association between childhood obesity and epilepsy or seizure
disorder.
RQ6: Is there an association between childhood obesity and epilepsy or seizure
disorder when controlling for socioeconomic status of parent, education level of parent,
income level of parent or guardian, and the age, race, and sex of child?
H06: There is no association between childhood obesity and epilepsy or seizure
disorder when controlling for socioeconomic status of parent, education level of parent,
income level of parent or guardian, and the age, race, and sex of child.
H16: There is an association between childhood obesity and epilepsy or seizure
disorder when controlling for socioeconomic status of parent, education level of parent,
income level of parent or guardian, and the age, race, and sex of child.
RQ7: Does the education level of the parent or guardian have a moderation effect
on the association between childhood obesity and cerebral palsy, Down Syndrome, and
epilepsy or seizure disorder?
H07: The education level of the parent or guardian does not have a moderation
effect on the association between childhood obesity and cerebral palsy, Down Syndrome,
and epilepsy or seizure disorder?

H17: The education level of the parent or guardian does have a moderation effect
on the association between childhood obesity and cerebral palsy, Down Syndrome, and
epilepsy or seizure disorder?
RQ8: Does the income level of the parent or guardian have a moderation effect on
the association between childhood obesity and cerebral palsy, Down Syndrome, and
epilepsy or seizure disorder?
H08: The income level of the parent or guardian does not have a moderation effect
on the association between childhood obesity and cerebral palsy, Down Syndrome, and
epilepsy or seizure disorder?
H18: The income level of the parent or guardian does have a moderation effect on
the association between childhood obesity and cerebral palsy, Down Syndrome, and
epilepsy or seizure disorder?
RQ9: Does the age of the child have a moderation effect on the association
between childhood obesity and cerebral palsy, Down Syndrome, and epilepsy or seizure
disorder?
H09: The age of the child does not have a moderation effect on the association
between childhood obesity and cerebral palsy, Down Syndrome, and epilepsy or seizure
disorder?
H19: The age of the child has a moderation effect on the association between
childhood obesity and cerebral palsy, Down Syndrome, and epilepsy or seizure disorder?

RQ10: Does the race of the child have a moderation effect on the association
between childhood obesity and cerebral palsy, Down Syndrome, and epilepsy or seizure
disorder?
H010: The race of the child does not have a moderation effect on the association
between childhood obesity and cerebral palsy, Down Syndrome, and epilepsy or seizure
disorder?
H110: The race of the child has a moderation effect on the association between
childhood obesity and cerebral palsy, Down Syndrome, and epilepsy or seizure disorder?
RQ11: Does the sex of the child have a moderation effect on the association
between childhood obesity and cerebral palsy, Down Syndrome, and epilepsy or seizure
disorder?
H010: The sex of the child does not have a moderation effect on the association
between childhood obesity and cerebral palsy, Down Syndrome, and epilepsy or seizure
disorder?
H110: The sex of the child has a moderation effect on the association between
childhood obesity and cerebral palsy, Down Syndrome, and epilepsy or seizure disorder?
Section 3 covers the accessibility of the original dataset, a detailed description of
the statistical analysis conducted, results of the data analysis plan and a conclusion and
summary of the answers to the research questions.

Accessing the Data Set for Secondary Analysis
I used archived data from The National Survey of Children’s Health 2018
database. Data were collected from June 2018- January 2019 (US Census Bureau, 2019).
The NSCH 2019 data were collected from June 28, 2019 to January 17, 2020 (US Census
Bureau, 2020). There were multiple ways for the participants to respond: web, paper,
Spanish translation, email, and telephone (US Census Bureau 2020). Of the five ways to
respond, there were two data collection instruments used the most; 20.2 % of respondents
utilized paper, and 78.8% of the respondents utilized the web (US Census Bureau, 2020).
There were no discrepancies in the use of the dataset from the plan presented in Section
2. My study used the following demographics: age, race, and sex of the child, and the
income and education level of the head of household/guardian. Included in the current
dataset were children between the ages of 0-17, both male and female, and of varied races
and ethnicities. The children were separated into three categories by their age at 0-5,
611, and 12-17. The current study had a sample of 582 children who met the criteria of
the study’s baseline. The study sample was determined after cleaning the data and
excluding the children who were not told they were overweight and did not have or were
ever told they had cerebral palsy, Down Syndrome, and epilepsy or seizure disorder.
When conducting the tests, the outcome variable (childhood obesity) was recoded as
0=No and 1=Yes. Data were analyzed between December 2022 and January 2023.
The original study conducted random sampling, so I was bound to that method as
a secondary data analyst. Because random sampling was used in the original study and
because I have controlling variables, my threat to validity was prevalent, which made

room for mistakes and additional tests. However, being that 100% of the population of
interest are children ages 0-17, the representation of the sample size was valid.
Study Sample
I originally determined that there would be a medium sample size once the
original data and population size of nearly 180,000 were analyzed. When answering the
research questions, the sample size decreased due to the dynamic of the research
question, the controlling variables, and the moderation of the variables. Since the data
has been cleaned and prepared for analysis, the sample size for this study was only 582,
which is less than 1% of the total study target population. Therefore, the sample size of
the current study was relatively small.
Results
Statistical Assumptions
The dependent variable was checked to make sure it was categorical, and the
values were no=0 and yes=1. The independent variables were also categorical. Missing
data and excluded data were removed. After the assumptions for using logistic
regression were met, the findings were developed.
Descriptive Statistics
Study Sample
The independent variables, cerebral palsy, Down Syndrome and epilepsy or
seizure disorder excluded the values of children who did not currently have one of the
intellectual or physical disabilities, as well as those who were not overweight. According
to the demographics table below (Table 5), there were 582 responses to the child’s sex,

race, and age, as well as the education and income level of the parent. There were 315
(54.1%) males and 267 (45.9%) females. The results also show there were 64 (11%)
Hispanics, 387 (66.5%) White, 59 (10.1%) Black, and 72 (12.4%) other. The age of the
children was categorized into three categories, and the results are as follows: 0-5 years at
121 (20.8%, 6-11 years at 201 (34.5%), and 12-17 years at 260 (44.7%).
This study also included the income and education level of the parents. With a
total of 582 responses and four categories, the education results are as follows: less than
high school 24 (4.1%), high school or GED 83 (14.3%), some college or tech school 169
(29%), and college degree or higher 306 (52.6%). With a total of 582 responses and 4
categories, the income results are as follows: 0-99% FPL 101 (17.4%), 100-199% FPL
122 (21%), 200-399% FPL 161 (27.7%), and 400% FPL or greater 198 (34%). There
were a total of 575 responses to whether the child was overweight or not. There were 64
(11.2%) parents who answered yes, and 511 (87.8%) parents who answered no. Note
that there were seven missing cases because they did not respond to the obesity question.
Descriptive analysis was conducted using frequency tests to determine the characteristics
of the study population.
Table 5
Study Population Descriptive Analysis (N=575)
Parameter N %
Obesity Yes
No
64
511
11.2%
87.8%
Sex Male
Female
315
267
54.1%
45.9%
Age
0-5 years
6-11 years
121
201
20.8%
34.5%

12-17 years 260 44.7%
Race/Ethnicity
Hispanic
White, Non-Hispanic
Black, Non-Hispanic
64
387
59
11%
66.5%
10.1%
Other 72 12.4%
Education
Less than High School
High School or GED
Some College or Tech School
24
83
169
4.1%
14.3%
29%
College Degree or Higher 306 12.4%
Poverty (Federal
Poverty Level,
FLP)
0-99%
100-199%
200-399%
101
122
161
17.4%
21%
27.7%
400% or Higher 198 34%
Inferential Statistics
To test the relationship between the independent variables and dependent variable,
a Chi-square, bivariate test was conducted for research questions 1-6. The pvalue and
Wald’s analysis were used to determine if there was an association between the outcome
variable and the IV’s. A 3-way Chi-square test was performed to identify the relationship
between the DV, IV’s, and confounding variables. Logistic regression was performed to
identify the odds of the IV and DV, when controlling for age, sex, and race of child, as
well as the income and education level of the guardian. To identify whether the DV and
IVs had a moderate effect on the confounding variables, I selected the lowest level
(interaction) of each confounding variable as a reference for the modifier. This was
conducted for research questions 7-11.

Research Questions & Hypotheses
Research question 1 is as follows: Is there an association between childhood
obesity and cerebral palsy? The alternative hypothesis was accepted as there was an
association between childhood obesity and cerebral palsy.
Research question 2 reads as follows: Is there an association between childhood
obesity and cerebral palsy when controlling for socioeconomic status of parent, education
level of parent, income level of parent or guardian, and the age, race, and sex of child?
The alternative hypotheses were accepted as there was an association between childhood
obesity and cerebral palsy, when controlling for socioeconomic status of parent,
education level of parent, income level of parent or guardian, and the age, race, and sex
of child.
Research question 3 reads as follows: Is there an association between childhood
obesity and Down Syndrome? The null hypotheses were accepted as there was no
association between childhood obesity and Down Syndrome.
Research question 4 reads as follows: Is there an association between childhood
obesity and Down Syndrome when controlling for socioeconomic status of parent,
education level of parent, income level of parent or guardian, and the age, race, and sex
of child? The null hypotheses were accepted as there was not an association between
childhood obesity and Down Syndrome, when controlling for socioeconomic status of
parent, education level of parent, income level of parent or guardian, and the age, race,
and sex of child.

Research question 5 reads as follows: Is there an association between childhood
obesity and epilepsy or seizure disorder? The null hypotheses were accepted as there was
no association between childhood obesity and epilepsy or seizure disorder.
Research question 6 reads as follows: Is there an association between childhood
obesity and epilepsy or seizure disorder when controlling for socioeconomic status of
parent, education level of parent, income level of parent or guardian, and the age, race,
and sex of child? The alternative hypotheses were accepted as there was an association
between childhood obesity and epilepsy or seizure disorder, when controlling for
socioeconomic status of parent, education level of parent, income level of parent or
guardian, and the age, race, and sex of child.
Research question 7 reads as follows: Does the education level of the parent or
guardian have a moderation effect on the association between childhood obesity and
cerebral palsy, Down Syndrome, and epilepsy or seizure disorder? The null hypotheses
were accepted as the education level of the parent or guardian did not have a moderation
effect on the association between childhood obesity and cerebral palsy, Down Syndrome,
and epilepsy or seizure disorder.
Research question 8 reads as follows: Does the income level of the parent or
guardian have a moderation effect on the association between childhood obesity and
cerebral palsy, Down Syndrome, and epilepsy or seizure disorder? The null hypotheses
were accepted as the income level of the parent or guardian did not have a moderation
effect on the association between childhood obesity and cerebral palsy, Down Syndrome,
and epilepsy or seizure disorder.

Research question 9 reads as follows: Does the age of the child have a moderation
effect on the association between childhood obesity and cerebral palsy, Down Syndrome,
and epilepsy or seizure disorder? The alternative hypotheses were accepted as the age of
the child did have a moderation effect on the association between childhood obesity and
cerebral palsy, Down Syndrome, and epilepsy or seizure disorder.
Research question 10 reads as follows: Does the race of the child have a
moderation effect on the association between childhood obesity and cerebral palsy, Down
Syndrome, and epilepsy or seizure disorder? The null hypotheses were accepted as the
race of the child did not have a moderation effect on the association between childhood
obesity and cerebral palsy, Down Syndrome, and epilepsy or seizure disorder.
Research question 11 reads as follows: Does the sex of the child have a
moderation effect on the association between childhood obesity and cerebral palsy, Down
Syndrome, and epilepsy or seizure disorder? The alternative hypotheses were accepted as
the sex of the child did have a moderation effect on the association between childhood
obesity and cerebral palsy, Down Syndrome, and epilepsy or seizure disorder. Tables
615 further explain and support the findings of the hypotheses for each research question.
Chi-Square Research Questions & Findings
Data were coded and entered in the SPSS software version 27 for analysis. As
previously stated, after cleaning the data and excluding some data, my sample size
included 582 participants. The Chi-square test is a non-parametric test used to determine
the relationships between two categorical variables; it was used to detect the association
between childhood obesity and cerebral palsy (RQ1). According to table 6, the
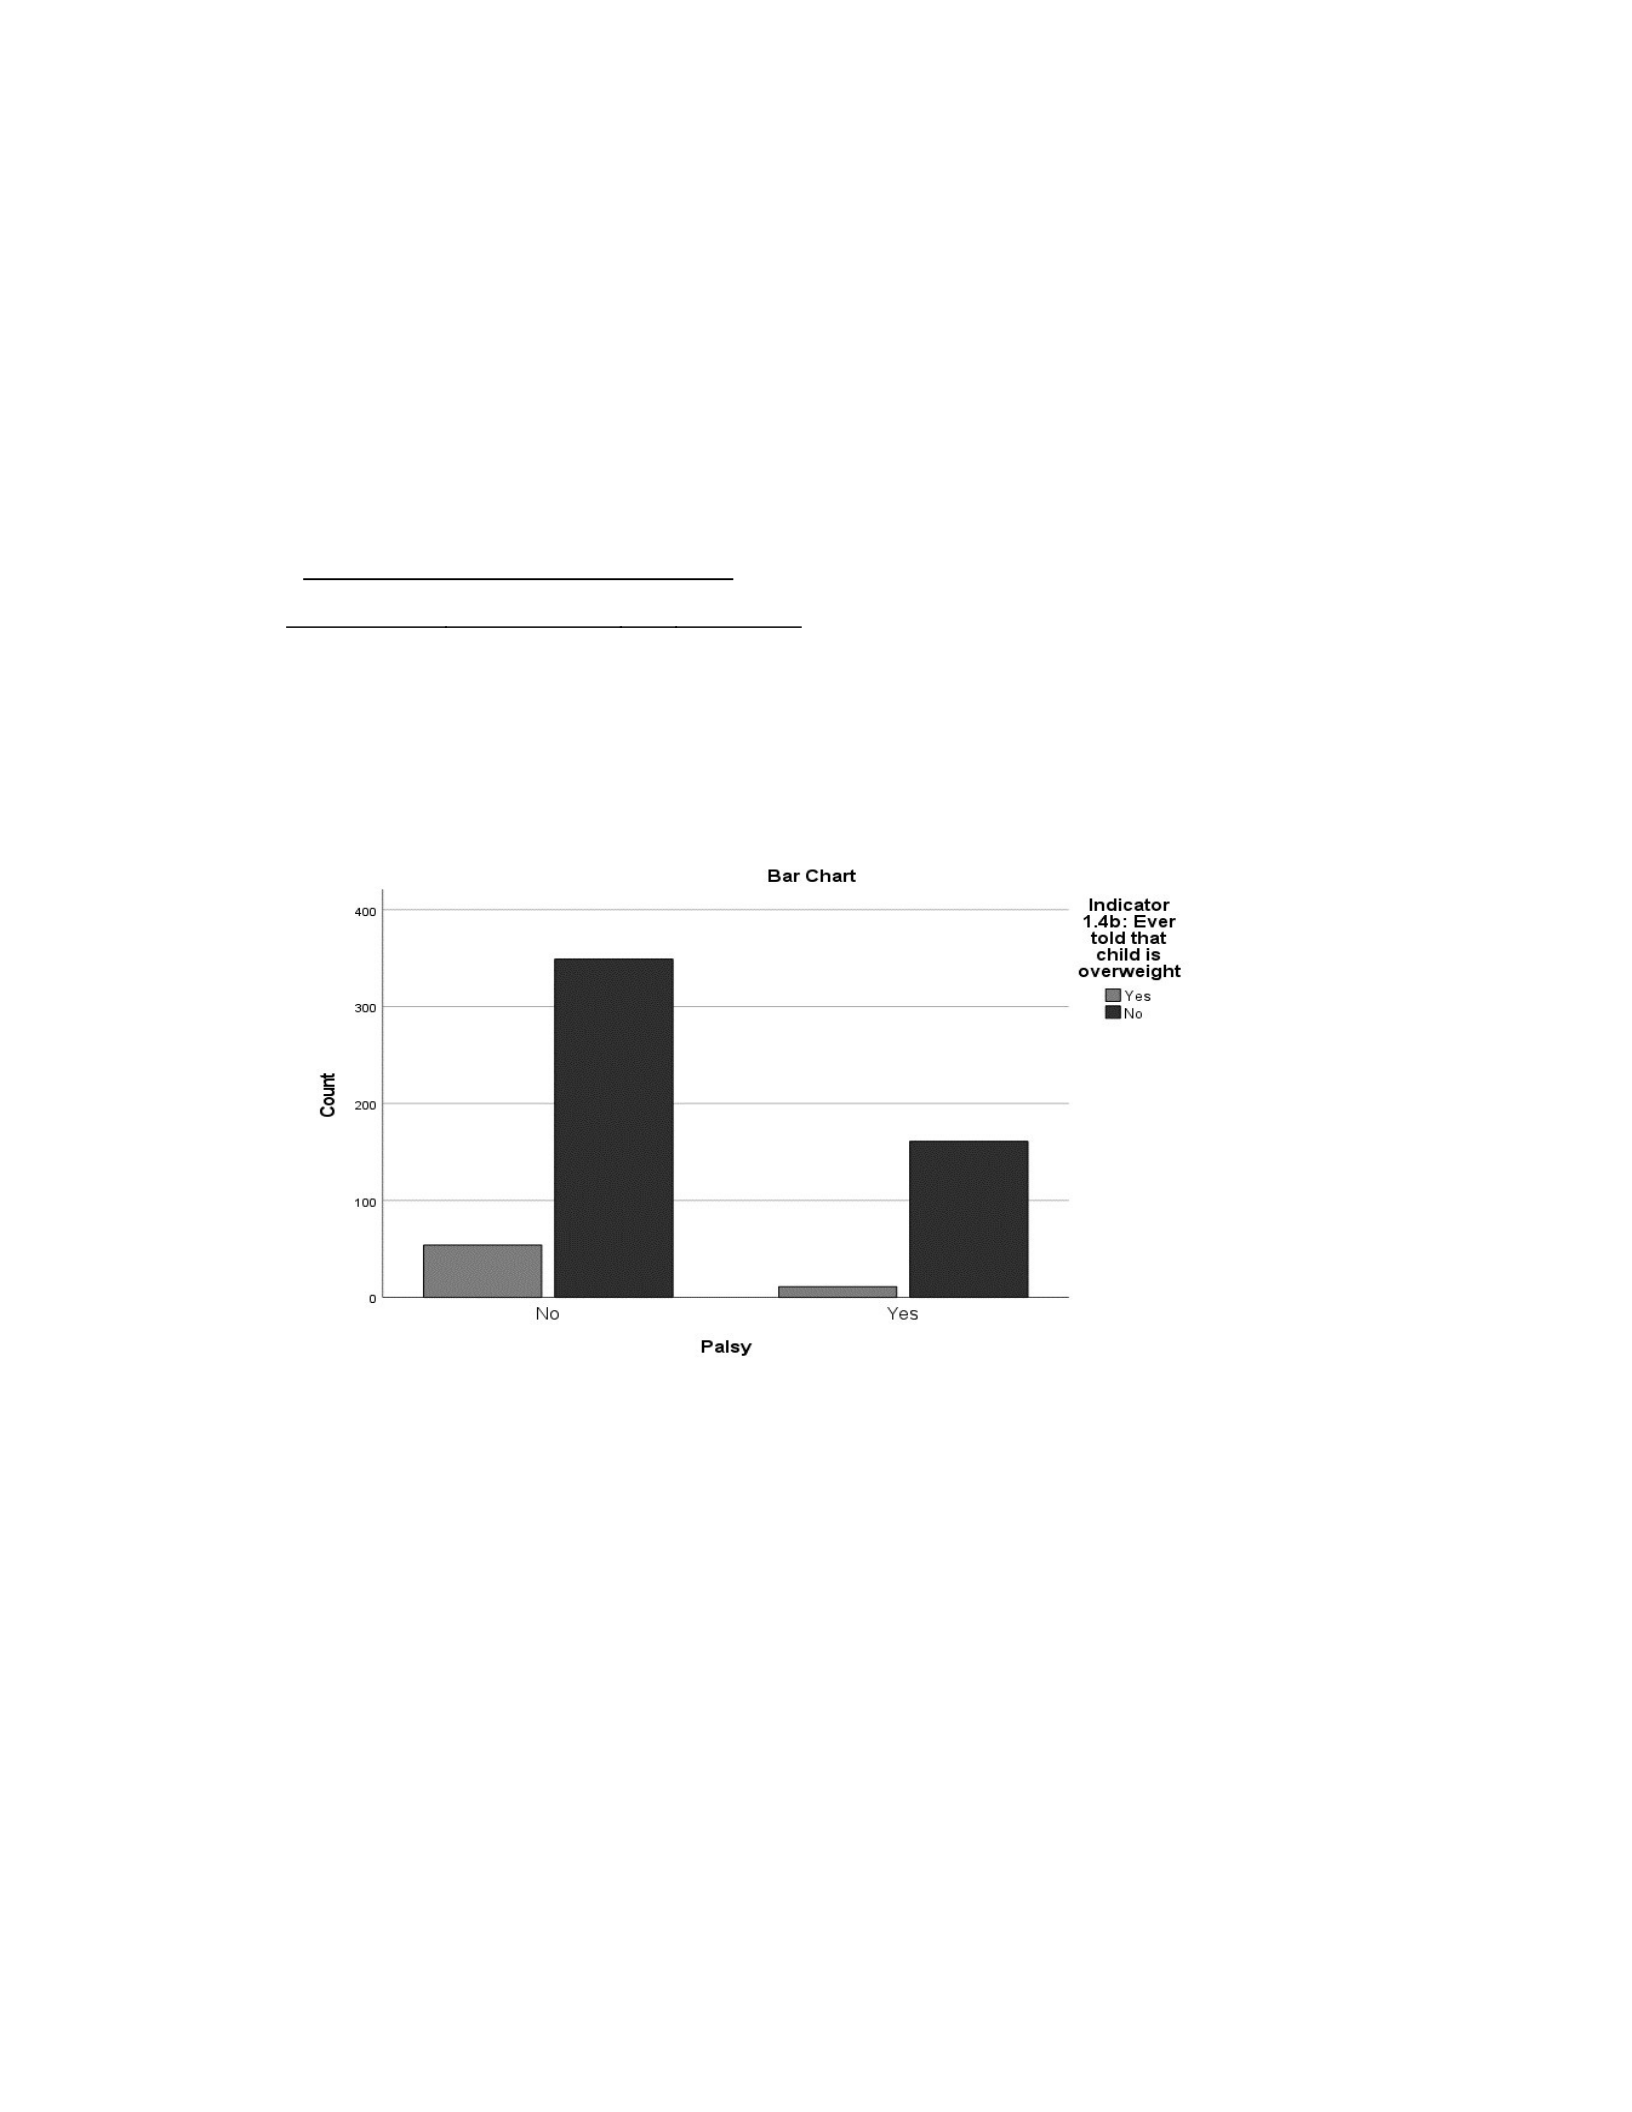
Chisquare test shows that there is a very weak association between childhood obesity and
cerebral palsy (Chi-Square= 5.88, df= 1, p-value= 0.040).
Table 6
Childhood Obesity & Cerebral Palsy (N=575)
Parameter Chi-Square df p-value
Palsy 5.88 1 0.040*
Figure 5
Association Between Childhood Obesity & Cerebral Palsy
A three-way Chi Square test was conducted to detect associations between the
demographics, cerebral palsy, and the outcome childhood obesity (RQ2). There were no
associations between childhood obesity and cerebral palsy controlling for gender. There
were no associations between childhood obesity and cerebral palsy with respect to
education level of parent. There were no associations between childhood obesity and
cerebral palsy with respect to income level of parent. There were no association between
childhood obesity and cerebral palsy with respect to age. However, there was a weak

association between a child who is overweight, has cerebral palsy, and is Hispanic
(ChiSquare= 4.205, df= 1, p-value= 0.040). All other ethnicities had no association with
a child who was overweight and has cerebral palsy (See Table 7).
Table 7
Childhood O
besity & Cerebral Palsy Controlling for Demographics of Child &
Socioeconomic Factors of Guardian (N=575)
Parameter Chi-Square Df p-value
Sex Male
Female
1.920
3.76
1
1
0.166
0.052
Age
0-5 years
6-11 years
1.12
1.63
1
1
0.290
0.202
12-17 years 3.147 1 0.076
Race/Ethnicity
Hispanic
White, Non-Hispanic
Black, Non-Hispanic
4,205
1,243
2.371
1
1
1
0.040
0.215
0.124
Other, Non-Hispanic 0.304 1 0.582
Education
Less than High School
High School or GED
Some College or Tech School
0.003 1.773
3.361
1
1
1
0.957
0.183
0.067
College Degree or Higher 1.509 1 0.219
Poverty (Federal
Poverty Level,
FLP)
0-99%
100-199%
200-399%
2.105 1.220
0.320
1
1
1
0.147
0.269
0.571
400% or Higher 2.684 1 0.101
The Chi-Square test was used to detect the association between childhood obesity
and down-syndrome (RQ3). There is no association between childhood obesity and
Down Syndrome (Chi-Square= .217, df= 1, p-value= 0.641), as the p-value is not equal
to or less than 0.05 (see table 8).

A three-way Chi Square was conducted to detect associations between the
demographics, Down-Syndrome, and the outcome childhood obesity (RQ4). According
to the results in table 9, there are no associations between childhood obesity and Down
Syndrome with respect to gender. There are no associations between childhood obesity
and Down Syndrome with respect to the race and ethnicity of the child. There are no
associations between childhood obesity and Down Syndrome with respect to the age of
the child. There are no associations between childhood obesity and Down Syndrome
with respect to the education level of the parent or guardian. There are no associations
between childhood obesity and Down Syndrome with respect to the income of parent.
Table 8
Childhood Obesity & Down Syndrome (N=575)
Parameter Chi-Square df p-value Down
Syndrome .217 1 0.641
Table 9
besity & Down Syndrome Controlling for Demographics of Child &
Socioeconomic Factors of Guardian (N=575)
Parameter Chi-Square Df p-value
Sex
Male
1.147
1
0.284
Female 0.049 1 0.825
Age
0-5 years
6-11 years
0.615
0.142
1
1
.0433
0.706
12-17 years
0.008
1
0.929

Race/Ethnicity
Hispanic
1.147
1
0.284
White, Non-Hispanic 0.049 1 0.825
Black, Non-Hispanic 2.47 1 0.619
Other, Non-Hispanic
0.004 1 0.949
Education
Less than High School
0.003
1
0.957
High School or GED 1.773 1 0.183
Some College or Tech School 3.361 1 0.067
College Degree or Higher
1.509 1 0.219
Poverty (Federal
Poverty Level,
FLP)
0-99%
2.105
1
0.147
100-199% 1.220 1 0.269
200-399% 0.320 1 0.571
400% or Higher 2.684 1 0.101
The Chi-Square test was used to detect the association between childhood obesity
and epilepsy or seizure disorder (RQ5). According to the following, there is no
association between childhood obesity and epilepsy or seizure disorder (Chi-Square=
.612, df= 1, p-value= 0.434) as the p-value is not equal to or less than 0.05 (see table 10).
A three-way Chi Square was also conducted to detect associations between the
demographics, epilepsy or seizure disorder and the outcome childhood obesity (RQ6).
According to table 11, there are no associations between childhood obesity and seizure
with respect to gender. There are no associations between childhood obesity and seizure

with respect to education level. There are no associations between childhood obesity and
seizure with respect to income of parent. There are no associations between childhood
obesity and seizure with respect to age. However, there is a weak association between a
child who is overweight, has epilepsy and are Hispanic (Chi-Square= 5.24, df= 1,
pvalue= 0.022). All other ethnicities did not have an association.
Table 10
Childhood Obesity & Epilepsy or Seizure Disorder (N=575)
Parameter Chi-Square df p-value
Epilepsy or Seizure Disorder 0.612 1 0.434
Table 11
besity & Epilepsy or Seizure Disorder Controlling for Demographics of
Child and Socioeconomic Factors of Guardian (N=575)
Parameter Chi-Square Df p-value
Sex
Male
0.044
1
0.844
Female 1.254 1 0.263
Age
0-5 years
0
1
0.983
6-11 years 0.134 1 0.714
12-17 years 0.580 1 0.446
Race/Ethnicity
Hispanic
5.24
1
0.022
White, Non-Hispanic 1.482 1 0.224
Black, Non-Hispanic 1.306 1 0.253
Other, Non-Hispanic 0.640 1 0.424
Education
Less than High School
3.725
1
0.054

High School or GED 0.550 1 0.458
Some College or Tech School 0.027 1 0.869
College Degree or Higher 0.023 1 0.879
Poverty (Federal
Poverty Level,
FLP)
0-99%
2.752
1
0.097
100-199% 0.438 1 0.508
200-399% 0.553 1 0.457
400% or Higher 0.097 1 0.755
Logistic Regression Research Questions & Findings
Research questions 7-11 answer the moderation effect association between
childhood obesity, cerebral palsy, Down Syndrome, and epilepsy or seizure disorder and
their association with the age, sex, and race of the child, as well as the income and
education level of the guardian. For research question 7, logistic regression was
performed to assess the interaction term of the parent education and cerebral palsy, Down
Syndrome and epilepsy moderation effect. According to table 12, there is no moderation
effect of education with cerebral palsy (Wald=0.043, p-value=0.835). The odds of
childhood obesity are not statistically significant for cases of cerebral palsy. There is no
moderation effect of education with Down Syndrome (Wald=1.369, p-value=0.242). The
odds of childhood obesity are not statistically significant for cases of Down Syndrome.
There is no moderation effect of education with epilepsy or seizure disorder
(Wald=2.654, p-value=0.103). The odds of obesity are not statistically significant for
cases of epilepsy or seizure disorder. Tables (19-21) in the appendix section show the
moderation effect of education by each education value.

Table 12
Logistic Regression and Moderation Analysis of Education and Cerebral Palsy, Down
Syndrome & Epilepsy or Seizure Disorder (N=575)
B S.E. Wald Sig. Odds Lower Upper
Interaction Education
.079 .379 .043 .835 .924 .439 1.944
*Cerebral Palsy
Interaction Education
.432 .369 1.369 .242 .649 .315 1.338
*Down Syndrome
Interaction Education
*Epilepsy or Seizure .541 .332 2.654 .103 1.718 .896 3.295
Disorder
For research question 8, logistic regression was performed to assess the
interaction term of the parents' income (poverty level) and cerebral palsy, Down
Syndrome, and epilepsy moderation effect. There is no moderation effect of income with
cerebral palsy (Wald=0.005, p-value=0.945). The odds of obesity are not statistically
significant for cases of cerebral palsy. However, the poverty level is statistically

significant compared to 0-99 FPL: poverty level 100-199 has an odds of 4.045 times 0-99
FPL (Wald=9.920, p=0.002); poverty level 200-299 has an odds of 2.311 times 0-99 FPL
(Wald=5.077, p-value=0.024); poverty level of 400 FPL and over has an odds of 2.887 0-
99 FPL (Wald=7.823, p-value 0.005). There is no moderation effect of income with
Down Syndrome (Wald=0.498, p-value=0.480). The odds of obesity are not statistically
significant for cases of Down Syndrome. However, the poverty level is statistically
significant compared to 0-99 FPL: poverty level 100-199 has an odds of 4.234 times 0-99
FPL (Wald=10.74, p=0.001); poverty level 200-299 has an odds of 2.633 times 0-99 FPL
(Wald=10.74, p-value=0.008); poverty level of 400 FPL and over has an odds of 3.253
099 FPL (Wald=9.527, p-value 0.002). There is no moderation effect of income with
epilepsy or seizure disorder (Wald=2.767, p-value=0.096). The odds of obesity are not
statistically significant for cases of seizure. Tables (22-24) in the appendix section show
the moderation effect of income by each income value.
Table 13
Logistic Regression and Moderation Analysis of Income and Cerebral Palsy, Down
Syndrome & Epilepsy or Seizure Disorder (N=575)
B S.E. Wald Sig. Odds Lower Upper
Interaction Poverty
-.021 .299 .005 .945 .980 .545 1.759
*Cerebral Palsy
Interaction Poverty
-.213 .301 .498 .480 .808 .448 1.459
*Down Syndrome
Interaction Poverty
*Epilepsy or Seizure .432 .260 2.767 .096 1.541 .926 2.565
Disorder

For research question 9, logistic regression was performed to assess the
interaction term of the child’s age and cerebral palsy, Down Syndrome, and epilepsy or
seizure disorder moderation effect. Per table 14, there is no moderation effect of age with
cerebral palsy (Wald=0.374, p-value=0.697). The odds of obesity are not statistically
significant for cases of palsy. However, the child’s age is statistically significant
compared to children 0-5 years of age: Age 6-11 has an odds of .246 times ages 0-5 years
(Wald=4.843, p=0.03); and Age 12-17 has an odds of 0.130 times ages 0-5 years
(Wald=10.6, p=0.001). There is no moderation effect of age with Down Syndrome
(Wald=0.374, p-value=0.541). The odds of obesity are not statistically significant for
cases of Down Syndrome. However, the child’s age is statistically significant compared
to children 0-5 years of age: Age 6-11 has an odds of .242 times ages 0-5 years
(Wald=4.687, p=0.03); and Age 12-17 has an odds of 0.106 times ages 0-5 years
(Wald=11.39, p=0.001). There is a moderation effect of age with epilepsy or seizure
disorder (Wald=2.050, p-value=0.033). The child’s age is statistically significant
compared to children 0-5 years of age: Age 6-11 has an odds of .272 times ages 0-5 years
(Wald=4.195, p=0.041); and Age 12-17 has an odds of 0.129 times ages 0-5 years
(Wald=11.3, p=0.001). Tables (25-27) in the appendix section show the moderation effect
of age by each age value.
Table 14
Logistic Regression and Moderation Analysis of Age and Cerebral Palsy, Down
Syndrome & Epilepsy or Seizure Disorder (N=575)
B S.E. Wald Sig. Odds Lower Upper
Interaction Age

-.248 .636 .151 .697 .781 .224 2.718
*Cerebral Palsy Interaction
Age
.334 .546 .374 .541 1.396 .479 4.069
*Down Syndrome
Interaction Age
*Epilepsy or Seizure .883 .617 2.050 .033 .488 .253 .944
Disorder
For research question 10, logistic regression was performed to assess the
interaction term of the child’s race and cerebral palsy, Down Syndrome, and epilepsy or
seizure disorder moderation effect. Table 15 shows there is no moderation effect of race
with cerebral palsy (Wald=0.155, p-value=0.097. The odds of obesity are not statistically
significant for cases of palsy. There is no moderation effect of race with Down
Syndrome (Wald=0.543, p-value=0.461). The odds of obesity are not statistically
significant for cases of Down Syndrome. There is no moderation effect of race with
epilepsy or seizure disorder (Wald=0.543, p-value=0.858). The odds of obesity are not
statistically significant for cases of epilepsy or seizure disorder. Tables (28-30) in the
appendix section show the moderation effect of race by each race value.
Table 15
Logistic Regression and Moderation Analysis of Race and Cerebral Palsy, Down
Syndrome & Epilepsy or Seizure Disorder (N=575)
B S.E. Wald Sig. Odds Lower Upper
Interaction Race
-.309 .417 .155 .694 .849 .375 1.921
*Cerebral Palsy
Interaction Race
-.309 .420 .543 .461 .734 .322 1.671
*Down Syndrome

Interaction Race
*Epilepsy or Seizure -.309 .420 .543 .858 1.068 .522 2.185
Disorder
For research question 11, logistic regression was performed to assess the
interaction term of the child’s sex and cerebral palsy, Down Syndrome, and epilepsy or
seizure disorder moderation effect. Table 16 shows there is a moderation effect of sex
with cerebral palsy (Wald=4.768, p-value=0.29). The odds of obesity are not statistically
significant for cases of cerebral palsy. However, the child’s sex is not statistically
significant (Wald=0.070, p=0.792). There is no moderation effect of sex with Down
Syndrome (Wald=0.812, p-value=0.368). The odds of obesity are not statistically
significant for cases of Down Syndrome. However, the child’s sex is statistically
significant compared to males: Female children have an odd of .467 times Males
(Wald=6.279, p=0.012). There is a moderation effect of sex with epilepsy or seizure
disorder (Wald=832, p-value=0.191). The odds of obesity are not statistically significant
for cases of epilepsy or seizure disorder. However, the child’s sex is not statistically
significant compared to males (Wald=.316, p=0.304). Tables (31-33) in the appendix
section show the moderation effect of sex by each sex value.
Table 16
Logistic Regression and Moderation Analysis of Sex and Cerebral Palsy, Down
Syndrome & Epilepsy or Seizure Disorder (N=575)
B S.E. Wald Sig. Odds Lower Upper
Interaction Sex
-.623 .299 4.768 .029 .520 .290 .935

*Cerebral Palsy Interaction
Sex
.603 .669 .812 .368 1.827 .492 6.781
*Down Syndrome
Interaction Sex
*Epilepsy or Seizure -.525 .576 .832 .191 1.829 .191 1.829
Disorder
Summary
In summary, the results show that there is a higher association between childhood
obesity and epilepsy and seizure disorder, and the confounding variables than the other
independent variables, cerebral palsy and Down Syndrome. Hispanic children ages 0-5,
who are overweight and epileptic are at a higher risk for other races and age groups. In a
recent study, being overweight was a common factor in children with intellectual
disabilities at a rate of 53.6% (Haegele et al., 2019). Moreover, epileptic overweight
children showed a weak significant relationship with Hispanics, age group 0-5, and
males. However, children with cerebral palsy also showed a weak significant association
between Hispanics and males. Understanding these aspects to this study can help to
implement measures to lower or decrease childhood obesity development in Hispanic
males.
Section 4 provides more information on the findings of the current study. It also
provides additional details on the nature of the current study as well as limitations and
recommendations for future studies and suggestions on potential social change.
Section 4: Application to Professional Practice and Implications for Social Change

Introduction
The purpose of this study was to examine whether there is an association between
childhood obesity and the selected physical and intellectual disabilities such as cerebral
palsy, Down Syndrome, and epilepsy or seizure disorder. Childhood obesity is a public
health topic that is widely discussed; however, there were a lack of studies conducted
regarding the specificities of this study. Some key findings of this study indicate that
there is a lack of association between childhood obesity and the independent variables, as
well as the controlling variables. Bivariate logistic regression tests were conducted for
research questions 1, 3, and 5, and multivariate logistic regression tests were conducted
for research questions 2, 4, and 6 due to the controlling variables. Because research
questions 7-11 were unique, a three-way Chi-square logistic regression test was
conducted to identify the relationship between the multiple variables.
Interpretation of the Findings
Previous research showed that there was no relationship between the parent’s
education level and the child’s weight (Reis et al., 2020). My study results also show that
there was no relationship between the parent’s education level and the child’s weight.
Previous research shows that there is a relationship between the parent’s income and the
child’s weight status (Bazán et al., 2018). According to the current study, there is no
association or moderation effect on the guardian’s income level and an overweight child
with a disability. Lastly, studies have shown that there is a relationship between the
child’s age and race and a child being overweight (Banks et al., 2016). However, my

study shows that there is no relationship between the child’s age, but there is a weak
association between race and an overweight child with cerebral palsy.
Theoretical Framework
I used the SCT and the HBM to help interpret the findings. The SCT is a popular
model used in the public health field to help understand the past experiences and behavior
of the participants (LaMorte, 2019). It was critical to understand the behaviors and
decisions of the guardians, as well as the children. The SCT was also helpful because it
supported the expectations of a disabled child and the outcome of their actions that will
affect their health. Lastly, the SCT was important to understand the observational
learning from the guardian. This model includes multiple levels of an individual’s
behavior and past experiences, as well as how they will make changes to their behavioral
health based on their social determinants of health (Rural Health Information Hub, 2018).
Overall, the SCT is used to navigate behavior change interventions (Rural Health
Information Hub, 2018). The SCT can support guardians who have children that are
overweight and have serious health issues such as cerebral palsy and epilepsy or seizure
disorder.
The HBM was important for this study because it supports the environmental and
socioeconomic status of the guardians. The model includes multiple levels of
psychological and behavioral capabilities of a person’s perceptions about something
(LaMorte, 2019). In the current study, the HBM focused on the perception of the
parent’s decisions for their child, based on their education level and income level, which
are in research questions 6 and 8. The current study determined that there was no

relationship between the socioeconomic status of the parent. That said, the perceived
beliefs and knowledge, cues to action and the self-efficacy constructs of the HBM
assisted in the possibility of a connection between the parent’s education and income
level and the child’s health status.
Limitations
There were several limitations to this study. One limitation was the fact that the
data could not be narrowed down to a specific state as the state data was not available.
This, in term, limits the location of children. Another limitation was that the dependent
variable was dichotomous. I was limited to the responses of the parents, so I do not know
if they answered truthfully or not. I was limited to knowing whether the children were
misdiagnosed or not. Previous studies conducted a correlational, quantitative study over
a long period of time; however, because a cross-sectional study was conducted, I was
limited to data collected for a short period of time. There was a large number of excluded
data, which may have limited the data for the parent’s education and income level, as
well as the data for the sex and race of the children. I had some violations, so I can’t
accurately interpret the results with a high level of certainty. I did not include the
parent’s history of cerebral palsy, Down Syndrome or epilepsy or seizure disorder.
Because I was limited to the age variable being categorical (0-5, 6-11, 12-17), there could
have been a particular age or ages that were significant, or at a higher risk versus others
within those categories. I also had less information with age being a categorical variable
versus being a continuous variable. Lastly, there were no stress factors presented, and

there was possibly a lack of resources provided to the parents/families that could have
been due to the environment.
Recommendations
Based on the findings and limitations of the study, I recommend that future
research be conducted on specific ages and in specific states, in relationship to children
with cerebral palsy, Down Syndrome, and epilepsy or seizure disorder. I also
recommend that further research be conducted on how and why overweight Hispanic
children are more prone to having cerebral palsy and epilepsy or seizure disorder.
Another suggestion would be to study the socioeconomic factors of an overweight child
who has cerebral palsy, Down Syndrome, and epilepsy or seizure disorder. Lastly,
additional research should be conducted with epilepsy as a standalone variable and not
combined with seizure disorder.
Implications for Professional Practice and Social Change
The concluding results of this study provided additional information about
childhood obesity and its relationship to physical and intellectual disabilities, including
socioeconomic controlling variables. From a public health professional perspective, it is
critical to focus on the improvement of overweight children and decrease the childhood
obesity prevalence rate of 49.7% (CDC, 2021). It is also important for health
professionals to conduct more interventions with children and parents of children who
have been diagnosed with cerebral palsy, Down Syndrome, epilepsy or seizure disorder,
and who are overweight. Public health professionals are frontline employees who help
to prevent diseases and improve the health of their communities through investigations,

evaluations, and surveillance (Otto et al., 2014). I believe that the HBM is a great tool for
public health professionals to help them understand and describe the perceptions of
people’s beliefs and behaviors regarding health issues. Public health professionals can
cultivate ideas about social behaviors and what factors play a role in those social
behaviors.
Based on the results of the study, childhood obesity has a connection with race,
epilepsy or seizure disorder, and cerebral palsy. Children who are overweight and have
been diagnosed with cerebral palsy should practice positive social change by eating
healthier and doing more physical activity. Parents or guardians of children with epilepsy
or seizure disorder should encourage their disabled child to take their medicine, as that
could promote positive health. It is with great hope that children who suffer from one of
the intellectual or physical disabilities listed in this study understand and seek the
professional care they need to promote longevity.
Public health professionals can assist in positive social change amongst those
living in a disabled environment by creating interventions that promote positivity that
will eventually decrease mortality in children who are diagnosed as overweight or obese.
Hopefully, this study shows Hispanic children and adults how important it is for them to
take care of their health. Lastly, public health professionals can tackle childhood obesity
and physical and intellectual disabilities through government funding, and by following
all policies and procedures when creating interventions, mailings, phone calls and
surveys to collect data.

Conclusion
The need for more research to be conducted on childhood obesity and cerebral
palsy, Down Syndrome, and epilepsy or seizure disorder remains. My purpose was to see
if there was some relationship between the outcome variable and the independent
variables, as well as the controlling variables. The association between childhood obesity
and cerebral palsy was faint, yet significant. The association between childhood obesity
and Down Syndrome was nonexistent. The association between childhood obesity and
epilepsy or seizure disorder was also nonexistent. However, there was a weak
association between Hispanics who were overweight and diagnosed with cerebral palsy,
as well as Hispanics who were overweight and diagnosed with epilepsy or seizure
disorder. There was no moderation effect on any of the variables combined. The
findings indicate that there is little to no association between childhood obesity and the
physical and intellectual disabilities used in the study.
The SCT was used to examine the outcome variable and to promote childhood
obesity prevention. The HBM was used to examine the health behaviors of the parents
and children. Both frameworks were used to answer the research questions in this study,
and to implicate the socioeconomic factors such as age, race, and sex of the child, and the
income and education levels of the guardian. These United States findings may be
similar to findings in other countries and may broaden the clinical research on these
disabilities and children who have them. Overall, childhood obesity does not have a
significant effect on children who have cerebral palsy, Down Syndrome, or epilepsy or

seizure disorder; however, more research is needed to understand the environmental
factors related to childhood obesity and the disabilities listed in this study.

