


1
Chapter 1: Introduction to the Study
The goal of this study was to examine the effectiveness of health information
based on social cognitive theory with obese and overweight women to reduce or
eliminate food addiction. Over the past 10 years, discussion of food addiction has been
increasing in academic journals (Davis et al., 2011). This has been due in part to the
expanding waistlines and increased body mass index (BMI) of the American public
(Goode, 2016) and the increased direct and indirect costs associated with being obese and
overweight (Martin, Hunter, Lauve, & O’Leary, 1995). Those who are obese and
overweight suffer from health complications and afflictions ranging from mild to severe
(Saltiel & Olefsky, 2017). Obese individuals suffer from diseases such as hypertension,
cancer, and diabetes (Persson, 2014). These afflictions lead to an increase in indirect and
direct medical health costs estimated at $147 billion (Colombi & Wood, 2011). Persson
(2014) estimated that almost 40% of Americans are obese.
The term food addiction is based on the addiction model. The addiction model is
defined as the need to consume certain substances even when they are known to be
harmful and detrimental to health (Volkow & Wise, 2005; West, 2001). The brain’s
pleasure centers perceive these addictive substances as a source of reward and pleasure,
and individuals experience stress or anxiety if they are unable to procure the addictive
substance (Volkow & Wise, 2005; West, 2001). Research on food addiction, addiction,
and obesity has resulted in a convergence and reframing of public and scientific
perspectives on addiction (Pedram et al., 2013, Sansone & Sansone, 2013; Volkow &
Wise, 2005). Instead of being confined to certain sources of reward (such as drugs),

2
addiction is now viewed as an intense and maladaptive desire for pleasure or stress
reduction regardless of the source of reward (Davis et al., 2011).
Researchers have identified certain food additives as significant contributors to
food addiction and overeating (Insawang et al., 2012; Lowndes et al., 2012). The two
significant food additives that have been identified in studies as significant contributors to
food addiction are monosodium glutamate (MSG) and high fructose corn syrup (HFCS)
(Insawang et al., 2012; Lowndes et al., 2012). In the current study, I examined the role
that these additives play in food addiction and obesity. Findings may provide an
opportunity to explore and apply social cognitive theory, which researchers have used
when focusing on addiction counseling and weight management, but have not applied in
food addiction.
Attempts to reduce expanded waistlines and BMIs that accompany food addiction
have resulted in successes and failures depending on the approach (Hebebrand et al.,
2014). One of the most promising approaches to weight loss is recognizing the role of
psychosocial support among people who are overweight and obese (Hogan, Linden, &
Najarian, 2002). Patients’ psychosocial support determines their ability to manage and
change their weight (Hogan et al., 2002). This knowledge includes but is not limited to:
health risks and food selection, goals, outcome expectations, and the ability to exercise
control to accomplish and maintain a task perceived as difficult or challenging
(Hopkinson, 2016). Social cognitive theory is designed to address these challenges
because the theory’s framework is related to acquiring and maintaining health behaviors
(Roche et al., 2012). Social cognitive theory focuses on promoting effective self-

3
management of health habits (Bandura, 2004). The components of social cognitive theory
have potential for encouraging self-management of health habits (Bandura, 2004).
In this study, I used key elements of social cognitive theory to create presentations
that delivered health information aimed at increasing knowledge and awareness of foods
and food additives that lead to food addiction and related symptoms. It was my hope that
increasing knowledge of the potential risks and outcomes of hazardous health behaviors
would initiated changes in health behavior. Over the course of 4 weeks, two groups of
women received different types of health information to reduce or eliminate food
addiction, as measured by the Yale Food Addiction Scale (see Appendix A). One group’s
presentations included health information that followed key elements of social cognitive
theory, such as self-efficacy, outcome expectations, incentive motivation, facilitation, and
self-regulation. Although there are other elements of social cognitive theory, these
particular elements have been highlighted in studies that have addressed behavioral
changes for those battling addiction (Fulton, Krank, & Stewart, 2012; Kelly & Greene,
2014; Kinsella, 2017; Patterson, Umstattd, Meyer, Beaujean, & Bowden, 2014; Soule,
Maloney, Guy, Eissenberg, & Fagan, 2017).
The second group received presentations of health information that were not
guided by social cognitive theory. For example, one week’s presentation addressed
reducing and eliminating symptoms of food addiction but did not mention self-efficacy or
ways to improve self-efficacy. I sent the presentations electronically every week. I
hypothesized that health information based on social cognitive theory would increase
participants’ knowledge of the effects of eating foods that contained MSG and HFCS,

4
and anticipated that the increased knowledge of food addiction and the food additives that
contribute to food addiction would evoke a precondition for change as participants
became more aware of the consequences of their health behavior (see Bandura 1997,
2004). The second group of women received a similarly worded presentation weekly, but
the presentation’s message was not based on social cognitive theory.
I invited participants to a weekly review of the health information delivered
online. These weekly reviews served three functions: (a) reduce participant attrition, (b)
increase the chances of study participants reading the health information, and (c) reduce
the likelihood of study participants not understanding the health information. To test for
anticipated changes in food addiction and food addiction symptoms, I administered the
Yale Food Addiction Scale (see Appendix A) to both groups as a pretest and posttest.
Both groups were surveyed twice (Week 1 and Week 4) using the Yale Food Addiction
Scale over the course of 4 weeks.
This study has the potential to yield a positive social change in three ways. First,
health professionals who treat obese and overweight individuals may better understand
food addiction’s role and influence on healthy behavior. Second, as health improves due
to better food choices and weight loss, obese and overweight individuals may experience
extended life expectancy, improved quality of life, and increased physical mobility
(Macchi, Russell, & White, 2013). Finally, cardiovascular disease risk factors, depression
and comorbid mental disorders, inflammation, and harmful cytokines may be reduced
(Kiernan et al., 2013; Wiltink et al., 2013).

5
In Chapter 1, I review literature on obesity and food addiction, including how
food additives such as MSG and HFCS play a role in contributing to food addiction by
subjecting obese and overweight people to suffer from symptoms such as food cravings,
overeating, depression, and anxiety. Also, I describe researchers’ use of health
information to change behavior. Chapter 1 also includes a discussion of social cognitive
theory and ways in which it has been used to modify food behavior. I also discuss gaps in
these studies, followed by an in-depth discussion of the research problem, which include
details on the study variables.
Background
Literature Related to Scope of Study
Based on my review of the literature, researchers had not examined obesity, food
addiction, and social cognitive theory in the same study. Many researchers published
studies that explored elements of social cognitive theory in weight management,
modifying food choices, and drug addiction (Dennis et al., 2001; Roche et al., 2012;
Walters et al., 2014). Perhaps one of the reasons researchers continue to examine the
potential of social cognitive theory is that social cognitive theory comprises tools that a
person needs to lose weight and fight addiction. Social cognitive theory provides
resources to increase knowledge to help individuals achieve certain behavioral goals in
the form of peer modeling or resources (Glanz, Rimer, & Viswanath, 2008, p. 173).
Social cognitive theory also helps individuals to address the psychosocial component in
the form of self-efficacy or outcome expectations. If used effectively, social cognitive

6
theory can be applied to a multitude of challenges for health professionals (Bandura,
2004; Glanz, Rimer, & Viswanath, 2008).
Researchers who have examined food addiction have also discovered that food
addiction is not a matter of simply exercising willpower when faced with certain food
choices. Many researchers have discovered people battling addiction (food or drug)
experience similar physiological changes (Barry, Clarke, & Petry 2009; Wilson, 2010).
For example, Barry et al. (2009) and Blaylock (1999) found that the addicted brain
undergoes a toxic chemical cascade that triggers cravings for and overeating of certain
foods. This chemical reaction does not take place in the unaddicted brain. Pivarunas and
Conner (2015) and Parylak, Koob, and Zorrilla (2011) discussed emotional changes that
have ranged from impulsivity, stress, anxiety, and depression stemming from food
addiction. Despite the physiological changes the body is subjected to, researchers have
found that using health information, coaching, and psychosocial theory to manage
symptoms of addiction (cravings, outcome expectations, motivation, and self-efficacy)
promotes behavioral change.
Gap in Knowledge in the Discipline
There are three gaps in knowledge in the discipline that I will address in this
study. First, I hope to address and increase the inclusion of participants into studies that
may be likely to benefit from the behavior change techniques (social cognitive theory-
based health information) used in this study. For example, Roach et al. (2003) found that
utilizing even one component of social cognitive theory (self-efficacy) in sharing health
information resulted in improvements in the eating behavior of study participants, even

7
though participants did not experience increased weight loss. The second gap in
knowledge in the discipline is how theory can be used to determine the selection of
behavior change strategies. I selected social cognitive theory for this study because many
components of the theory are conducive to individuals contemplating or engaging in
behavioral change. The final gap in knowledge is using theory to tailor behavioral change
techniques to quasi-experiments. Prestwich et al. (2014) stated that the theory could be
used to accentuate constructs or types of individuals who should be targeted in studies.
Need for This Study
This study is needed because there is limited research that examines changes in
food addiction and symptoms by comparing the differences between groups of obese and
overweight women in which one group has been exposed to health information that is
based on the constructs of social cognitive theory and the other group has been exposed
to non- social cognitive theory-based health information. Specifically, few researchers
have examined managing the symptoms of food addiction (such as cravings, anxiety,
overeating, and guilt) with behavior-promoting theories such as social cognitive theory to
improve food choice behavior.
Additional reasons this study is needed are the potential benefits to medical
professionals and counselors that treat the obese because it will allow these professionals
to understand behavioral change. For medical professionals who conduct research by
searching online databases, once this study has been completed and uploaded to the
online databases, the medical community will become aware of a new way to apply the
constructs of social cognitive theory towards treating the symptoms of food addiction.

8
Also, professionals will become aware of the constructs of social cognitive theory’s
potential role in autonomous self-regulation and sustained behavioral change over time–
useful tools in weight loss (Gorin, Powers, Koestner, Wing, & Raynor, 2014). Over time,
as overweight and obese individuals lose weight, they will benefit by experiencing
extended life expectancy, improved quality of life, and increased physical mobility
(Macchi et al., 2013). Finally, another potential health benefit to individuals includes
clinically significant improvements in cardiovascular disease risk factors, and reduction
of depression, comorbid mental disorders, inflammation, and harmful cytokines (Kiernan
et al., 2013; Wiltink et al., 2013).
Problem Statement
Individuals who are overweight and obese may struggle with food addiction and
the accompanying symptoms, such as food cravings, feelings of guilt, and overeating
(Yeh et al., 2016). These symptoms drive those who are overweight and obese to exhibit
poor food choice behavior (Leahey et al., 2012). Despite abundant sources of information
made available by public health agencies, and posting nutrition information on food
labels, almost 70% of Americans are overweight and obese (Fortuna, 2012). In efforts to
study food addiction and nutrition, previous researchers have found similarities between
the body’s response to illicit drugs and certain foods (Zhang et al., 2011). These findings
indicated that certain foods (such as those that contain the addictive substance MSG and
HFCS) trigger an addictive and negative chemical cascade in the body (Blaylock, 1999).
This chemical cascade usually results in overeating and cravings (Barry et al., 2009;
Rolls, 2007). Social cognitive theory comprises key constructs that have the potential to

9
manage the symptoms of food addiction and help weight loss efforts. I anticipated that
providing health information based on social cognitive theory would lead to changes in
food addiction.
There are three pieces of evidence that the problem is current, relevant, and
significant to the discipline. The first is that both Davis et al. (2011) and Meule and
Kübler (2012) found that food addiction is a significant contributor to the obesity
epidemic and accompanying comorbidities. The second piece of evidence is that those
who are food addicted suffer from higher bouts of depression and anxiety (Davis et al.,
2011). These higher bouts of depression and anxiety are partially due to the inability of
the food-addicted person to secure the food reward (Chao et al., 2017). The final piece of
evidence is that food addicts report that they experience stronger cravings as well as
feelings of guilt or anxiety than their non-food-addicted counterparts (Davis et al., 2011;
Parylak et al., 2011). One component of social cognitive theory, called facilitation
potentially, addresses this issue by recommending tools and resources that would enable
a person to cope with these feelings and symptoms.
Investigators have shown that food addiction has taken more of a priority in
research due to increased national BMI and obesity levels (Davis et al., 2011). Davis et
al. (2011) and Pivarunas and Conner (2015) stated that food addiction should be listed as
a classifiable condition that exhibits clinical symptom and psychobehavioral aspects that
are similar to drug abusers. Finally, overeating, a key symptom of food addiction, is
triggered by the inability to regulate emotions (Pivarunas & Conner, 2015).

10
Although researchers have linked food addiction to highly palatable foods such as
pasta and processed confections, researchers have not examined a link to the chemicals
that are often added to these types of foods, such as MSG and HFCS. Parylak et al.
(2011) stated that those who ether label themselves as food addicted or rank as food
addicted according to the YFAS often consume pasta and processed confections. In
addition, researchers have not attempted to use a psychological theory as a catalyst for
behavior change to address food addiction.
Purpose of the Study
Obese and overweight individuals who suffer from food addiction face physical
challenges and suffer psychological anguish before, during, and after adopting healthier
food behavior (Eyres, Turner, Nowson, & Torres, 2014). The purpose of this quasi-
experimental study was to test the theory that food addiction can be changed, reduced, or
eliminated by using several components of social cognitive theory with health
information provided via electronic presentations. One component of social cognitive
theory states that knowledge of health threats and health benefits create a precondition for
change (Bandura, 2004). I created a precondition for change for study participants when
they read the health information contained in the presentations. The presentations
increased study participants’ awareness of food addiction and factors that contribute to
food addiction, such as MSG and HFCS, and associated symptoms (health threat). The
presentations also communicated the health benefits of avoiding foods that promote food
addiction. Taking this approach modeled the outcome expectations component of social
cognitive theory. Outcome expectations potentially impacted study participants’ health

11
behavior (see Bandura, 2004). Defining outcome expectations is also important because
individual motivation is influenced when individuals see how adopting recommended
health behaviors serves their self-interest (Bandura, 2004).
The participants were overweight and obese women from a private school in
Chicago, IL and Walden University’s online participant pool. I created two groups and
gave participants in both groups pretests and posttests. I exposed one group to health
information materials not based on social cognitive theory, while the other group
received health information materials based on social cognitive theory. This occurred
over the course of 4 weeks. The health information based on social cognitive theory
included nutrition information and tips on healthy eating. I had a significant focus on
avoiding foods containing HFCS and MSG as well as recommendations for the most
commonly consumed foods that do not contain HFCS or MSG, with messages worded to
reflect concepts in social cognitive theory such as self-efficacy, outcome expectations,
and peer modeling.
The dependent variables were food addiction and food addiction symptom count.
The dependent variable of food addiction was defined by scores from the Yale Food
Addiction Scale (see Appendix A) that indicated food addiction when participants
selected three or more criteria in addition to one of two clinical significance items
indicating that the participant had experienced impairment or distress. I noted a potential
for food addiction if participants indicated (by circling the specific food item) that they
have a problem with processed foods (ice cream, doughnuts, cookies, cake, candy, white
bread, rolls, and soda). I also noted a potential for food addiction if participants listed

12
certain foods or food brands with labels that list MSG or HFCS in their list of ingredients.
The presence of MSG or HFCS in these cases was confirmed by identifying the product
online via the manufacturer’s website and identifying MSG or HFCS in the list of
ingredients. The sum of the seven diagnostic criteria indicated food addiction symptom
count.
Research Questions and Hypotheses
The research questions (RQs) and hypotheses were the following:
RQ1: What is the extent of the difference in food addiction posttest scores (while
controlling for any differences at pretest) as measured by the Yale Food Addiction Scale,
among overweight and obese women who receive health information based on social
cognitive theory compared to overweight and obese women who receive health
information not based on social cognitive theory?
H01: When comparing the impact of social cognitive theory-based health
information with non-social cognitive theory-based health information presented to
overweight or obese women, there is no significant difference in food addiction posttest
scores (while controlling for differences in pretest scores) as measured by the Yale Food
Addiction Scale.
HA1: When comparing the impact of social cognitive theory-based health
information with non- social cognitive theory-based health information presented to
overweight or obese women, there is a significant difference in food addiction posttest
scores (while controlling for differences in pretest scores) as measured by the Yale Food
Addiction Scale.

13
RQ2: What effect does health information based on social cognitive theory
have on symptom count posttest scores, as measured by the Yale Food Addiction Scale,
among obese and overweight women compared to obese and overweight women who
receive health information not based on social cognitive theory?
H02: When comparing the impact of social cognitive theory-based health
information with non-social cognitive theory-based health information presented to
overweight or obese women, there is no significant difference in symptom count posttest
scores as measured by the Yale Food Addiction Scale.
HA2: When comparing the impact of social cognitive theory -based health
information with non-social cognitive theory-based health information presented to
overweight or obese women, there is a significant difference in symptom count posttest
scores as measured by the Yale Food Addiction Scale.
The independent variable was health information delivered electronically that was
either based on social cognitive theory or not based on social cognitive theory. The
independent variable, according to Creswell (2009), is a variable that “causes, influences,
or affects outcomes” (p. 50). The two types of health information I used in this study fit
Creswell’s definition because they would potentially cause the dependent variable, food
addiction as measured by the Yale Food Addiction Scale, to change.
According to Bandura (2004), social cognitive theory comprises a core set of
determinants, the mechanism through which they work, and the optimal ways of
translating this knowledge into effective health practices. These determinants include
possessing knowledge of certain health risks and seeing the advantage and benefit of

14
adopting certain beneficial health behaviors (Bandura, 2004). If individuals are unaware
of how their health behavior is affecting their health, they will have very little reason or
motivation to change their health behavior (Bandura, 2004). In the current study, the
electronic presentation for the treatment group was designed to increase awareness of
health behaviors that contribute to food addiction. The presentation provided information
about exercising control over the environment and health behavior, which was the self-
efficacy component of social cognitive theory. Health information pertaining to setting
goals, expected challenges adopting new behavior, and benefits of adopting healthy
behaviors to overcome food addiction addressed the outcome expectations component of
social cognitive theory. I presented this information electronically to treatment group
participants over the course of 4 weeks. To ensure comprehension of the information
presented in the presentations, I reviewed health information presented in the presentation
for that week in a prerecorded weekly webinar.
Theoretical Framework
Two theories provided the framework for this study. The first theory was food
addiction theory. The second theory was social cognitive theory. These theories
addressed the physical and psychological perspectives of what transpires when food is
ingested, and why implementing and maintaining healthy food behaviors is challenging.
Food addiction theory was the cornerstone of this study. Humans are predisposed
to desire and seek foods that are fatty and sweet (Davis et al., 2011). In prehistoric times,
this benefited humans by ensuring their survival when food was scarce. However, a

15
predisposition toward these foods in times when food is no longer scarce leaves humans
vulnerable to overeating and obesity.
Food addiction has been gaining ground in both the media and in scientific
research circles due to increased weight gain in the United States (Davis et al., 2011).
Indirectly related to the addiction model, food addiction describes an individual’s
inability to modify behavior and food intake while exhibiting addictive behaviors
(Joranby, Pineda, & Gold, 2005; Val-Laillet, Layec, Guerin, Maurice, & Malbert, 2011;
Zhang et al., 2011). Although food addiction and general drug addiction are similar, food
addiction is different from other addictions. Illegal drugs are not essential to live, but the
consumption of food is critical. Associated with the brain’s reward system and striatal
dopamine receptors, the addiction model plays a role in obesity and how the brain reacts
to drug addiction (Wilson, 2010). The loss of control resulting in overeating is
reminiscent of drug intake patterns seen in those addicted to drugs and has led researchers
to describe these actions when combined with obesity as food addiction (Volkow, Wang,
Tomasi, & Baler, 2013).
It is essential to append the Food Addiction Theory with information about MSG
and HFCS. Highly processed and palatable foods such as cakes, ice cream, and fast foods
often contain these food additives, and contribute significantly to the food addiction and
obesity epidemic (Blaylock, 1999). For instance, foods that contain MSG act upon the
brain’s reward system receptors, thus mimicking the addiction model as the person
overeats to achieve the same “high/food high”–like a drug addict. This overeating, in
turn, leads to feelings of guilt, shame, anxiousness, and depression (Davis et al., 2011).

16
An approach that could serve as a catalyst and act as a pre-condition for change by
informing someone that suffers from food addiction about the foods that trigger
overeating and how to manage the symptoms of food addiction would be helpful.
Finally, the theoretical foundation for the proposed study is founded upon key
components of Bandura’s Social Cognitive Theory. According to Bandura (2004), social
cognitive theory focuses on promoting effective self-management of health habits to
ensure success with the newly learned behavior. Social cognitive theory has many
constructs that empower a person to implement behavioral change because it focuses on
psychosocial components of a person’s personality that drive motivation, such as self-
efficacy, reciprocal determinism, incentive motivation, self-regulation, and outcome
expectations (Bandura, 1969; Glanz, et al., 2008).
Nature of the Study
Researchers have indicated that the components of social cognitive theory show
promising results in weight loss studies (Ince, 2008; Netz & Raviv, 2004; Petosa,
Suminski, & Hortz, 2003). Social cognitive theory also has shown promising results in
studies designed to increase physical activity over the course of several weeks (Ince,
2008; Netz & Raviv, 2004; Petosa et al., 2003). To measure progress, researchers have
chosen repeated-measures designs such as ANCOVA to compare the participant
responses over the duration of a study. Researchers have also used a pretest and a posttest
to compare differences and changes between groups. For example, Gorin et al. (2013)
used a behavioral weight loss program to examine the long-term impact of a
comprehensive, home-focused weight loss study. Gorin et al. (2013) compared the

17
differences in weight changes of participants exposed to their behavioral weight loss
programs. Only participants received treatment in one group, and in the second group
participants and their living partners received treatment. This study was conducted over
the course of 18 months with 201 participants. Gorin et al. (2013) selected an ANCOVA
as their measurement approach and used weight and age as the covariates. Like Gorin et
al. (2013), I chose to compare differences between two groups. I followed the same
approach by selecting a repeated-measures ANCOVA. The pretest was used as the
covariate to gauge whether the posttest scores changed because of the health information
presentation. Doing so allowed comparison of food addiction scores between one group
of participants exposed to health information based on social cognitive theory and
another group exposed to health information not based on social cognitive theory.
The second element of the rationale for the selected design is based on this study
being quasi-experimental in nature, because study participants were purposively assigned
to groups. I alternately assigned participants to groups based on the order in which they
signed up for the study. I used groups from a private school in Chicago, IL and Walden
University’s online participant pool. According to Creswell (2009), researchers select a
quasi-experiment and nonrandom approach because only a convenience sample is
available. For this study, the convenience sample comprised the participant pool from a
private school in Chicago, IL and Walden University’s online participant pool.
The third element of this study’s design was selecting survey methodology to
gather the desired data. I used a demographic questionnaire (see Appendix B) and a
survey instrument (Yale Food Addiction Scale; see Appendix A) to collect data from

18
participants. Demographic data included factors such as age, weight, height,
socioeconomic status, and ethnicity to describe the sample and to calculate BMI. I used
BMI to identify obese and overweight participants. The demographic questionnaire also
inquired about dieting habits, mental health, and anxiety. SurveyMonkey (2015)
deployed the survey instrument, which was an electronic version of the Yale Food
Addiction Scale. There were two reasons I selected the electronic survey format. First,
administering the instrument and demographic questionnaire electronically was more
cost-effective (see Groves et al., 2009); compared to administering the survey via mail,
the cost for a survey administered via the Internet is lower. Second, surveys allow a
researcher to collect large amounts of data privately in a short period (Creswell, 2009).
Survey participants had an increased sense of privacy in this study because the surveys
were administered electronically, which gave study participants an opportunity to select a
comfortable and secure location to answer survey questions (see Groves et al., 2009).
When study participants are allowed the opportunity to share their responses
anonymously, the responses tend to more accurately reflect the survey taker’s true
perspective or state of health (Storey et al., 2009). In addition, I obtained ethics approval
from Walden University’s institutional review board (IRB) before contacting prospective
study participants (Approval Number 05-03-18-0326424).
The methodology for this study was quasi-experimental. The inclusion criteria
were women who (a) were at least 18 years of age, (b) had a BMI over 25, and (c) were
not pregnant or had not given birth in the last 6 months. I invited people of all ethnic and

19
cultural backgrounds to participate and excluded participants who did not fit the sampling
frame for the study.
I collected data by recruiting a convenience sample of overweight and obese
women from a private school in Chicago, IL and Walden University’s online participant
pool. I calculated participants’ BMI when they provided information about their height
and weight, and compared this information to a BMI chart from the Centers for Disease
Control and Prevention (CDC, 2014). If the information provided by the participants fit
the overweight and obese category, I extended an invitation to potential participants to
participate in the study. Potential study participants completed a screening questionnaire
and provide informed consent via e-mail.
Using the online survey software SurveyMonkey, I collected data from 84
overweight and obese female participants over the age of 18. A minimum of 68 study
participants was required to detect a difference in food addiction between groups, as
measured by the Yale Food Addiction Scale. I informed participants that the study would
be 4 weeks in duration, would take place online, would address the influence of health
information on food addiction and consumption, and would include demographic
information. I analyzed data using IBM SPSS 25 statistical software.
Definitions
Craving: A state of mind in which the person is continually occupied with intense
thoughts and desires of a certain substance or food that compels and motivates the person
to seek and consume a particular substance (usually drugs) that is difficult to resist. For

20
the purpose of this study, craving referred to food craving (Kemps et al., 2008; Martin,
O’Neil & Pawlow, 2006).
Food addiction: The condition in which certain foods, whether seen or eaten,
activate the same brain circuitry that is activated by addictive drugs, and thereby regulate
dietary behavior (Rogers, 2011).
High fructose corn syrup (HFCS): Meyers, Mourra, & Beeler (2017) defined high
fructose corn syrup as a liquid that is metabolized differently than other sugars. Unlike
fructose, which is absorbed easily by the body and responsive to insulin, high fructose
corn syrup passes through the body and is not responsive to insulin. High fructose corn
syrup contains 55% fructose, 42% glucose, and 3% other saccharides (Meyers et al.,
2017). The food industry began by adding HFCS to improve food palatability (Rolls,
2007). Although food palatability was improved, researchers subsequently revealed that
consumption of HFCS reduces the brain’s ability to detect leptin/satiety signals, resulting
in metabolic syndrome, overeating, and obesity (Gucciardi, 2011).
Ghrelin: A hormone and neuropeptide (Stoyanova & le Feber, 2014) responsible
for appetite stimulation, weight gain, reward, mood, learning, and memory by secreting
an activating growth hormone in the stomach and parts of the brain such as the pituitary
gland, hypothalamus, cortex, brain stem, and hippocampus (Costantini et al., 2011;
Stoyanova & le Feber, 2014). Absence or reduced level of ghrelin in the human body
results in decreased appetite (Fiszer et al., 2010).
Obese: Individuals are classified as obese when they reach a BMI of over 30,
(CDC, 2014). A female is classified as obese when her body fat percentage is over 32%

21
(WebMD, 2003). Finally, a female is classified as obese once her waist measurement
reaches or exceeds 35 inches (CDC, 2014).
Overweight: Individuals are classified as overweight when they reach a BMI of
over 25 (CDC, 2014). There is no classification for overweight in the body fat category,
only obesity.
Leptin: A 167-amino-acid peptide hormone that is released from white adipocytes
and reflects a person’s total body fat mass (Darbandi et al., 2012). Leptin is produced by
brown fat tissue, the placenta, ovaries, skeletal muscles, the stomach, mammary epithelial
cells, bone marrow, the pituitary gland, and the liver (Darbandi et al., 2012). This
hormone is directly responsible for appetite stimulation; without it, unbridled food
consumption would take place (Darbandi et al., 2012).
Monosodium glutamate (MSG): An excitotoxin that functions by improving food
flavor (Blaylock, 1999). MSG is present in prepared foods such as soups, chips, fast
foods, frozen foods, and canned goods. MSG is often disguised in food labels under
alternative names such as hydrolyzed vegetable protein, vegetable protein, natural
flavorings, and spices.
Self-efficacy: A person’s expectations and belief in his or her ability to execute
certain behaviors successfully (Bandura, 1997).
Assumptions
There were four assumptions in the study. First, I assumed that participants would
answer survey questions honestly. Second, I assumed that those who are obese and
overweight also experience food addiction. My third assumption was that all study

22
participants consume foods that contain certain amounts of MSG and HFCS. Last, I
assumed that study participants participated in this study because they were motivated to
improve their health by managing the symptoms of food addiction, and were interested in
finding a way to lose weight.
These assumptions were necessary to acknowledge the role of human nature and
how it may affect survey participants. Survey participants are usually aware of societal
expectations and social desirability when answering survey questions, and are prone to
bias and inaccurate memory (Johns & Miraglia, 2015; Rhoads & Rhoads, 2012). Second,
it was important to be aware of factors that could impact the effectiveness of health
information based on social cognitive theory, such as motivation and self-efficacy (see
Kelly & Greene, 2014; Senécal, Nouwen, & White, 2000). Even if participants have the
right information, those lacking the ability to believe in their abilities to accomplish
certain tasks (self-efficacy) will not be as successful as participants with higher levels of
self-efficacy (Berndt et al., 2013).
Scope and Delimitations
Those who suffer from food addiction are battling two unconventional
physiological battles in the effort to control their weight and eating habits. First,
individuals experiencing food addiction report a range of symptoms from food cravings
to anxiety until the desired food item has been obtained (Parylak et al., 2011). Second,
once the consumption of the food has commenced, dopamine emitted by the brain’s
pleasure centers overcome all reasoning, and individuals find themselves in a hedonistic
fueled need to overeat (Nasser, 2001). The research problem and challenge for this study

23
is reducing or eliminating food addiction by applying the social cognitive theory.
Therefore, there are two specific aspects of the research problem that I addressed in the
study. First, this study helped overweight or obese study participants gain knowledge
about new behavioral approaches to making better food choices. This in turn resulted in a
change in weight control skills. I accomplished this by exposing overweight and obese
study participants to the study’s social cognitive theory-based health information
presentations which were delivered weekly electronically over the course of four weeks.
Second, this study improved study participant level of food addiction.
An important facet of the research problem that I addressed in the study is
comparing current levels of food addiction versus anticipated changes to food addiction
in the future by conducting a pre-test and a post-test. I used repeated-measures ANCOVA
for several reasons. First, there were two groups in the study receiving health
information, but over the course of four weeks, only one group was exposed to social
cognitive theory-based health information. The second group received generalized health
information that was not been customized with social cognitive theory (this group will
receive the social cognitive theory-based health information after the study). Because I
surveyed study participants repeatedly and compared differences between the scores, I
used a repeated-measures ANCOVA for this study.
This study included a convenience sample of female participants from Walden
University’s online participant pool. Therefore, the study results may not be generalizable
to men. Moreover, there was the potential for self-selection bias, as those that are truly
food addicted may not identify themselves as food addicted. Finally, another limitation

24
was time and the inability to investigate the effects of social cognitive theory-based
health information on food addiction for a more substantial amount of time.
The area of potential generalizability to others is possible to the extent they reflect
the population given that this is a convenience sample. For example, using
SurveyMonkey required a certain level of computer literacy by study participants. This
placed a limit on my ability to generalize my findings and apply these study results to
those that may not be computer literate. The area of potential generalizability would
come from the ability to apply the study findings to study participants. I succeeded in
using social cognitive theory-based health information to address food addiction
challenges, there is a possibility that these findings could be duplicated in other studies
with success. Another area of potential generalizability is applying the results to morbidly
obese women. Due to the components of social cognitive theory, such as providing
participants with the tools needed to overcome external stimuli, there could be potential
to apply these principles to morbidly obese female study participants to examine how
they respond. For example, this study provided definitive information that included
healthier food choices that can be used as a substitute for the foods that promote obesity
and overeating. This is a valuable approach because those who are obese cite various
reasons for being obese. These reasons include lack of accessibility to healthier food
options, food cooked in excess fat, claims that oil tastes better, and eating to the point of
satiation was a higher priority than the nutritional value of food consumed (Caamaño et
al., 2016; Witkos, Uttaburanont, Lang, & Arora, 2008).

25
Limitations
In conducting this study, I took the following limitations into account. The study
population will likely include people with some level of college education to ensure that
participants understand survey questions and health information materials presented. The
sample consisted of overweight and obese participants, and may not be generalizable to
people who have a body fat percentage or BMI within normal range. For example, Meule
and Kübler (2012) conducted a study on food addiction using individuals who were
healthy size and found that food addiction was positively correlated with a higher BMI.
However, Meule and Kübler (2012) admitted that a limitation of their study was that it
lacked overweight and obese individuals. Similar to Meule and Kübler’s (2012) study, I
conducted this study only on a certain segment of the population (women); as a result,
findings will not be generalizable to men.
This study focused on those with some level of college education; therefore, the
results may not be generalizable to individuals with a high school diploma or lower. The
sampling frame for the target population was female, overweight or obese, are not
currently pregnant, or pregnant in the last six months. I used convenience sampling in this
research study because of the availability of the sampling units (Frankfort-Nachmias &
Nachmias, 2008). Participation in this study was be voluntary, therefore, for the purpose
of this research, I selected the sample because obese and overweight women are needed
for the study, and the private school in Chicago, IL and Walden University online
participant pool is convenient.

26
The Yale Food Addiction Scale measures food addiction by asking about eating
habits over the past year. Examples include ice cream, chocolate, white bread, pizza, and
french fries. The overconsumption of foods of this nature often causes feelings of guilt
(Joranby et al., 2005; Kemps et al., 2008). This has the potential to introduce response
bias if study participants underreport information. An additional possibility for study bias
is non-response bias, which entails nonresponses on surveys (Creswell, 2009).
I addressed these biases by increasing the sample size to offset any nonresponse
bias (Davern, 2013). Also, was no option available to skip or not answer survey questions
(SurveyMonkey, 2015). Because the survey asked about what some consider a sensitive
topic (food consumption), there was a concern about whether survey participants will
answer questions honestly. One way this was overcome to encourage honest answers
from participants was by reassuring them that I will hold their answers in the strictest
confidence. I included a message in the survey that reassured study participants of the
confidentiality of their responses. Another way honest answers were encouraged from
study participants was by having them answer survey instrument questions via a
computer from the comfort of a location of their choosing (i.e. home/mobile phone).
According to Stevens-Watkins and Lloyd (2010), there was an increase in the number of
survey questions that study participants answered honestly when they were not required
to answer sensitive questions in front of an interviewer. A second way that I addressed
biases was to implement Lanyon and Wershba’s (2013) suggestion based on their study
of underreporting response bias.

27
Significance
Previous researchers have used components of social cognitive theory to drive
positive health behaviors, such as treating drug addiction, alcohol addiction, and smoking
cessation programs (Bricker et al., 2010). Researchers have also applied the components
of social cognitive theory to weight management programs and increasing fruit and
vegetable intake (Basen-Engquist et al., 2013; McCabe, Plotnikoff, Dewar, Collins, &
Lubans, 2015; Roche et al., 2012). There are two potential contributions of this study that
will advance knowledge in this discipline. First, modeling health information featured in
this study upon key facets of the components social cognitive theory created a
precondition for change that initiated changes in health behavior. Second, participants
learned how to apply components of social cognitive theory as preventative health
measures and initiatives. Having knowledge of potential health risks and the benefits of
implementing or following certain healthy practices can create the conditions that are the
precondition for changing one’s behavior (Bandura, 2004). Preconditions for change
were applied to this study as well, because I made study participants aware of the
potential health risks of consuming foods containing HFCS and MSG, food addiction,
and how to cope with the symptoms of food addiction.
Potential Contributions of the Study
This study will advance practice or policy by helping professionals learn the role
physiology and psychology play for overweight and obese people in their attempts to
modify their food intake behavior. Researchers have stated that poor diet contributes to
obesity and early death, which can be prevented by adopting healthier eating habits and

28
behaviors (Meule & Kübler, 2012). Those who review this study will learn a different
approach to applying a psychological theory to health information.
Potential Implications for Positive Social Change
Potential implications for positive social change include helping the scientific
community gain a deeper understanding of the significance of food addiction and how it
affects food consumption choices. Parlesak and Krömker (2008) stated that even an
increased awareness of the impact of the nutrition and effects of certain foods would
improve eating habits. Finally, there is the potential for applying components of social
cognitive theory to improve behavior outcomes for health promoting programs.
Summary
In conclusion, in this study, I presented evidence that food addiction and the
overeating that accompanies food addiction have remarkable similarities to drug
addiction. I have cited multiple clinical trials as evidence of the biological underpinnings
that drive food and drug addiction. I have also shared commonalities between food
addiction and drug addiction. However, food addiction and the overeating that results
because of this affliction makes food addiction unique, as the body requires food to live,
whereas it does not require other addictive substances, such as drugs, making food
addiction straddle the line between substance addiction and behavioral addiction, as it
encompasses characteristics of both. On one hand, foods rich in fat, sugar, and salt
unleash a dopamine-charged response that acts on the brain and other pleasure centers of
the body in the same way as an addictive drug. On the other hand, consuming food is a
pleasurable activity with its own hedonistic-like rewards. Therefore, it was important to

29
examine the behavioral component of food addiction for individuals that are obese and
overweight, which is why it was important to introduce components of social cognitive
theory to address the symptoms of food addiction. It was also important to evaluate
changes in food addiction using the Yale Food Addiction Scale.
In chapter 2, I will provide a literature review on various causes of obesity. This
will include food addiction, genetics, and the environment, and will also discuss food
addiction and social cognitive theory−the theoretical constructs of this study. I will
conclude the chapter with potential implications and societal benefits of research on food
addiction, weight management, obesity, and behavioral-based theories like the model
used for this study–social cognitive theory.

30
Chapter 2: Literature Review
In this literature review, I restate the problem and purpose by discussing social
cognitive theory as it relates to weight management, food addiction, and using health
information to encourage a change in behavior. The obesity epidemic has been increasing
and has led to efforts by public health authorities to increase prevention programs
(Frederick, Saguy, & Gruys, 2016; George et al., 2017). Social, physiological, and
environmental factors contribute to obesity, thereby making it a complex issue to resolve.
Meanwhile, food addiction has gained increased attention in the scientific community.
Food addiction can be explained in part by attribution theory, which pertains to an
individual’s locus of control over behavior (Korn, Rosenblau, Rodriguez Buritica, &
Heekeren, 2016). People who suffer from food addiction experience neurological activity
that is similar to the neurological activity of a person addicted to illicit drugs (Hardy,
Fani, Jovanovic, & Michopoulos, 2018; Zhang et al., 2011). Although the various
properties of food (flavor, fat content, and texture) sometimes make it challenging to
measure the behavioral responses and neurological responses in obese and overweight
individuals, research has emerged that indicates certain food ingredients promote
addictive behavior (Blaylock, 1999). These ingredients, MSG and HFCS, favorably effect
food by enhancing taste, texture, and palatability, which causes a loss of locus of control,
leading to overeating. When this loss of control occurs, overweight and obese people and
those who suffer from food addiction experience feelings of shame, depression, guilt, and
anxiety (Meseri, Bilge, Kücküerdönmez, & Altintoprak, 2016; Rasmussen, 2015).

31
Therefore, it is important to examine not only social cognitive theory and food addiction,
but the food ingredients that contribute to food addiction: MSG and HFCS.
Synopsis of the Current Literature
This study was based on two theoretical frameworks. The first, food addiction
theory, is related to addiction theory. Food addiction refers to an individual’s inability to
modify behavior and food intake. The behavior exhibited is similar to other addictive
behaviors because dopamine levels of the brain are affected (Joranby et al., 2005; Val-
Laillet et al., 2011; Zhang et al., 2011). Those who suffer from food addiction often
consume highly palatable foods, which leads to overeating. The second theoretical
framework was social cognitive theory, which comprises (a) awareness of the desired
health outcome; (b) knowledge, which is the precondition for change, and (c) self-
efficacy. Bandura (1997, 2004) stated that acquiring knowledge of a dangerous issue,
health challenge, or situation, creates a precondition for change. In this study, I presented
participants with health information that provided knowledge of food addiction, its
influence on the body, how it impacts weight management, and how certain foods
containing MSG and HFCS play a role in obesity. I anticipated that alerting food-
addicted individuals of harmful ingredients such as MSG and HFCS that their
precondition for change would be activated (see Bandura, 1997, 2004; Connor-Greene,
1993). In turn, they would more receptive to health information that would teach them
how to avoid foods containing harmful ingredients (see Bandura, 1997, 2004; Connor-
Greene, 1993). The cornerstone of these two theories is awareness. I anticipated that once
study participants became aware of how the foods they eat contribute to overeating and

32
weight gain (increased dopamine levels in the brain and reduced detection of satiety
signals from the stomach), it would set up a precondition for change. Providing health
information featuring components of social cognitive theory may increase motivation to
change behavior patterns and decrease food addiction.
In the following literature review, I describe obesity, causes of obesity, risk
factors, and influencers of obesity. I also review studies about the effect of obesity on
health, society, and comorbidity. I describe food addiction and define it in greater detail,
as well as its biological effects and psychological impact on behavior. Because of its
impact on the ability to adhere to positive food consumption behaviors, I also discuss
cravings and key branches of social cognitive theory such as self-efficacy, outcome
expectations, and incentive motivation. In addition, I discuss the relationship between
foods containing HFCS and MSG and obesity. I explain how past research related to this
study and describe the objectives and variables.
Literature Search Strategy
Library databases and search engines were used to access digital resources and
physical books. Databases included PsycINFO, MEDLINE, CINAHL & MEDLINE
Simultaneous Search, Nursing & Allied Health Source, ScienceDirect, PsychARTICLES,
PsycTESTS, and ProQuest. Additional resources included references from the World
Health Organization (WHO), Centers for Disease Control and Prevention (CDC), and
other governmental websites.
The search terms used to conduct the literature search included food addiction,
Yale Food Addiction Scale, social cognitive theory, observational learning, peer

33
modeling, facilitation, drug addiction, high fructose corn syrup, monosodium glutamate,
overeating, craving/food cravings, addiction, leptin resistance, self-efficacy, weight
loss/weight management, diet, and behavior change. I saved copies of digital journals and
governmental websites in both electronic and hard copy formats.
Most of this literature review was conducted using a 7-year scope. There were
two exceptions. The first exception was literature about social cognitive theory. The
second exception was in the Yale Food Addiction Scale, the instrument used for this
study.
I handled cases for which there was too little current research, and few (if any)
dissertations or conference proceedings, in three ways. First, I expanded the search
beyond the 7-year scope. In some cases, the search yielded additional studies both
directly and indirectly related to the topic. Second, I procured books related to the topic
and extracted additional information that pertained to the search term (or terms) in
question. Finally, I used offshoot terms. For example, if a cited article listed a certain
search term that was not used in previous searches, then the new search incorporated the
new search term.
Theoretical Foundation
This study was based on two theories: social cognitive theory and food addiction
theory. I chose these theories because they provided a unique perspective to not only the
obesity epidemic, but also the approach and tools needed to develop a solution. This
study was important because researchers often create effective solutions involving
instruments, programs, and information that promote changes in health behavior that are

34
crafted using theoretical premises and frameworks that contain the elements needed to
facilitate a solution.
Social cognitive theory is based on the complexity and capacity of the human
mind to process information, and the biases that play a role in behaviors that are gained
through observations, experiences, and communication (Bandura, 1986; Glanz et al.,
2008). Social cognitive theory is based on reciprocity in the form of interactions guided
by a person between his or her environment (Anderson et al., 2006; Bandura, 1986;
Glanz et al., 2008). The theory shows that people have the ability to determine their
environment for their purposes (Glanz et al., 2008). According to Bandura (1986),
advanced cognitive capability coupled with flexibility enables an individual to create
ideas transcending his or her sensory experiences. Bandura also argued that forethought
plays a pivotal role in motivation.
Social cognitive theory is based on nine key concepts. The first is reciprocal
determination, which pertains to environmental influences on a person’s behavior
(Bandura, 1986; Glanz et al., 2008). Reciprocal determination entails individuals’
behavior precipitated by their beliefs and the environment. An ideal example of wayward
reciprocal determination occurred in the 16th century. Before Galileo discovered the
world is round, those who wished to explore and sail would avoid sailing past a certain
point in the ocean for fear of falling off the face of the earth. In this case, false belief, (the
world is flat) in addition to the avoidant behavior, (don’t sail too far away in the sea) kept
blind to corrective reality (sail beyond what is perceived to be the edge of the ocean and
discover that the ship will not fall off the edge of the earth). Meanwhile, this false belief,

35
coupled with avoidant behavior created a “reciprocating triadic loop” between
individuals’ false beliefs, their avoidant of reality behavior, and corrective reality.
The second concept of social cognitive theory is outcome expectations. Outcome
expectations pertain to individuals’ beliefs about the consequences of their choices and
actions (Bandura, 1986; Glanz et al., 2008). An example of outcome expectations would
entail changing expectations about the taste associated with eating nutritious food.
A third and often highly studied concept of social cognitive theory is self-
efficacy. Self-efficacy pertains to possessing the belief in one’s ability to execute
necessary behavior for a desired goal (Bandura, 1986; Glanz et al., 2008). An example of
self-efficacy entails individuals’ beliefs in their ability to control pain. People handles
pain much better when they believe that they have the ability to control pain versus
someone who is subjected to pain without the ability to control it (Bandura, 1997).
The fourth concept of social cognitive theory is collective efficacy, which entails
one believing in one’s group’s ability to execute necessary behaviors for desired goal
(Glanz et al., 2008). An example of collective efficacy could entail the effect of a cogent
public health message. An effective public health message that evokes positive emotions
about tackling health maladies is fortuitous because it makes people (the collective) feel
efficacious about their beliefs of being able to embrace healthy practices that will address
health aliments (Bandura, 1997).
The fifth important concept of social cognitive theory is observational learning.
An example of observational learning may entail a musician observing a peer playing a
new piece of music. The musician then visualizes rehearsing and reviewing the musical

36
piece (Bandura, 1986). While visualizing, the musician’s fingers imitate the keystrokes
necessary to execute the musical piece. Finally, the musician plays the musical piece.
Thus, one learns a new behavior via direct experience through peer modeling and
cognitive rehearsal (Bandura, 1986; Glanz et al., 2008).
The sixth concept of social cognitive theory is incentive motivation, which entails
modifying behavior using punishment or praise to achieve desired behavioral outcomes
(Glanz et al., 2008). An example of incentive motivation for children and adults might
entail toilet training a preschooler. Bandura (1997) stated that physical impact of many
activities determines how the activity will be executed because people will go to great
lengths to reduce or eliminate aversive conditions and gain physical comfort. In the case
of a toilet training preschooler, to avoid the aversive condition and discomfort of soiled
clothing, the preschooler will train faster if he/she wears toddler underwear versus
training pants or diapers (Vereckey, 2009).
The seventh component of social cognitive theory is facilitation, which describes
one possessing the necessary tools to easily accomplish certain goals (Glanz et al., 2008).
Giving several recipes (tools) featuring important foods to assist a dieter in making better
food choices would be an example of facilitation.
The eighth component of social cognitive theory addresses the ability to control
oneself and monitor one’s actions. This component–self-regulation–entails enabling one
to enact control by utilizing various means (Bandura, 1986; Glanz et al., 2008). Examples
may include goal setting and rewarding oneself when desired behaviors are demonstrated
(Bandura, 1986; Glanz et al., 2008).

37
The final component of social cognitive theory is moral disengagement, which
entails dehumanizing people by disengaging self-regulating moral standards Glanz et al.
(2008). The 79% rise of the presence in cyberbullying is an example of moral
disengagement (Underwood & Ehrenreich, 2017). Victims of cyberbullying are
associated with and experience behavior such as low self-esteem, loneliness, and low
academic achievement (Underwood & Ehrenreich, 2017).
Source, Origin, and Theoretical Foundations of Food Addiction Theory
The consensus among researchers is that food addiction is similar to drug
addiction from the perspective of the neurological changes to the brain. The commonly-
observed addictive agents are foods containing high fat and high sugar, which is
prevalent in processed foods, according to researchers conducting studies on rodents
(Liebman, 2012; Ziauddeen & Fletcher, 2013). Emerging research on food addiction
theory has surpassed labeling broad categories of highly palatable foods that are sources
of high fat and sugar as being the culprits. Research now links specific food additives
such as MSG and HFCS, which are added to foods to extend shelf life and increase
desirability (Barry et al., 2009; Zhang et al., 2011). As research into food addiction
theory began to gain more ground, researchers also discovered that although certain foods
have a propensity to incite food addiction, some food additives increase the potential for
food addiction in people who possess certain vulnerabilities (such as those who are
overweight and obese).
Major theoretical propositions. There are three major theoretical propositions.
The first is based on a component of social cognitive theory that states that knowledge

38
creates a pre-condition to change one’s behavior (Bandura, 1997/2004). The second is
that once a person is receptive to changing his or her behavior, providing the necessary
tools via portions of social cognitive theory to foster and nurture the behavioral change
will increase the person’s self-efficacy and motivation compared to those who do not
possess the necessary tools. The third major theoretical proposition is that by reducing the
amount of not only highly palatable foods, but highly palatable foods containing MSG
and HFCS, the symptoms of food addiction will be reduced or eliminated.
Assumptions. Despite the immense availability of studies that have examined
food addiction theory, utilizing health information to change food consumption behavior,
and utilizing components of social cognitive theory for weight management and addiction
treatment, these studies suffer from three limitations. The first concerns the lack of a
thorough analysis of distinct qualities of addictive foods when high fat and high sugar
foods have been identified as a substantial contributor to food addiction theory. This
deficiency is especially important in light of researchers stating that high fat and high
sugar foods most likely contain the food additives MSG and HFCS (Collison et al., 2010;
Martin et al., 1995; Ren, Ferreira, Yeckel, Kondoh, & de Araujo (2011). Understanding
the likelihood that these foods contain these ingredients as well as foods such as ice
cream, fast foods, processed foods, and condiments is essential. It could also potentially
provide a set of implementation guidelines for health practitioners who are working to
address overweight and obese populations.
Also, I will delineate several assumptions that are appropriate to the application of
the theories that are the foundation of this study. In chapter one, I stated that one

39
assumption is that study participants will provide honest answers and feedback to
instrument questions. This is important not only to the study, but also to the results.
Another assumption that is appropriate is that study participants will participate in this
study because they are motivated to improve their health by managing the symptoms of
food addiction, and that they are interested in finding a way to lose weight.
The second limitation pertains to studies that utilize health information to bring
about behavioral change. In these studies, there has been an inability to apply strategy
and theory consistently. The lack of strategy and theory is unfortunate, because the
research reports provide an incomplete or vague description of research outcomes−for
example, Kinzie (2005) stated that their research outcome would be to “demonstrate
observable effectiveness,” (p. 3-5).
The final limitation concerns utilizing components of social cognitive theory for
weight management and addiction treatment. Although studies have measured various
components of social cognitive theory, most studies focus on self-efficacy, few studies
work to integrate a majority of components of social cognitive theory into the health
messages that are provided to study participants (Basen-Engquist et al., 2011). For
example, Roach et al., (2003) conducted a weight loss study for adults, which included a
health education component. Although considerable attention and many sections of the
literature were dedicated to health education information, self-efficacy was allocated only
one section. However, incorporating even a small amount of self-efficacy into this study
yielded improvements in eating behavior compared to the control group (Roach et al.,
2003). Another limitation concerning utilizing components of social cognitive theory

40
observed in other studies are researchers focusing on the health benefits of weight loss or
preventing certain health conditions instead of directly mentioning potential
improvements in body image (Poddar, Hosig, Anderson-Bill, Nickols-Richardson, &
Duncan, 2012).
How the theory has been applied previously. This section explains and provides
a literature- and research- based analysis of how the theories have been applied
previously in ways similar to this current study. This section will discuss how
components of social cognitive theory have been applied to weight loss studies. Because
food addiction is a form of addiction, this section will also discuss how components of
social cognitive theory have been applied to reduce and eliminate symptoms of addiction.
Finally, this section will explore studies that have used behavioral theories to address and
reduce the symptoms of food addiction.
Social cognitive theory and weight loss. Components of social cognitive theory
have been applied previously and in with similar methodology to the current study in
three ways. The first is helping to reduce the consumption of prepared and processed
foods. In a study carried out by Nollen et al. (2008), study participants lost weight by
applying components of social cognitive theory to change their health behavior and diet
choices. The second method, (also a frequently utilized way with most studies) is to use
the self-efficacy component of social cognitive theory to bring about behavioral change
(Kiernan et al., 2013; Olander et al., 2013; Springfield et al. 2015). For example,
Springfield et al. (2015) designed a weight loss intervention guided by social cognitive
theory that focused on the self-efficacy component of social cognitive theory by

41
increasing participants’ sense of self-efficacy to improve study outcomes. Finally, Clark,
Abrams, Niaura, Eaton, and Rossi (1991), conducted a study on self-efficacy
expectations among obese populations and utilized the Weight Efficacy Life-Style
Questionnaire to measure obese participants’ self-efficacy judgments about their eating
behaviors.
Researchers have applied components of social cognitive theory in three ways.
The first was during a study that examined social cognitive theory’s effect on quitting and
reducing addiction desires (Heydari, Dashtgard, & Moghadam, 2014). Heydari et al.
(2014) sought to eradicate addiction by utilizing components of social cognitive theory
such as personal efficacy, self-regulatory process, and self-efficacy. Haydari et al.
provided information on addiction, its complications, and treatment, followed by health
information that was designed to inspire feelings of vulnerability by changing study
participants’ attitude about addiction and the associated health risks. Finally, in the self-
efficacy stage, study participants were taught problem solving, self-projection, and
communication skills (Heydari et al., 2014). To measure the effectiveness of the social
cognitive theory -based information, the researchers provided a post-test questionnaire,
and measured the difference between the two groups using ANOVA. Connor, Gullo,
Feeney, Kavanagh, & Young (2014) applied components of social cognitive theory in
similar ways to the current study using a different method. In their study, Connor et al.
utilized self-efficacy and outcome expectations to address symptoms of addiction among
cannabis users. They found that when health information was provided to cannabis
addicts, the patients’ ability to cope with urges decreased (Connor et al., 2014). Finally,

42
in a study designed to increase health awareness for those who suffer from cardiovascular
disease, Petrogianni et al. (2013) found participants experienced an increase in self-
efficacy and improved diet and physical activity levels.
Behavioral change theory and food addiction. Although there is an abundant
amount of research that discusses the entomology of food addiction, research that
pertains to reducing the symptoms of food addiction is lacking. To date, there are no
studies that have used social cognitive theory to address food addiction. Therefore, to
identify a study similar to this study, I sought out studies using behavioral change
theories to address food addiction. Although research was lacking in this area as well, a
few studies did emerge. Burmeister, Hinman, Koball, Hoffmann, and Carels (2013) found
that those who suffered from food addiction were undermined in their weight loss efforts
because of eating-related and addiction pathologies, such as body shame and feelings of
withdrawal. Many researchers studying addiction have explored weight loss through
various means, such as reduced calorie consumption (Martin et al., 1995), and various
high-calorie foods such as cheesecake and chocolate (Kenny, 2013) and chocolate
milkshakes (Blum, Gardner, Oscar-Berman, & Gold, 2012). Very few researchers have
tried to identify the extent of food addiction in human populations using scientific criteria
and focusing on foods containing addictive substances such as MSG and HFCS (Collison
et al., 2010; McCabe & Rolls, 2007).
Mason et al. (2015) utilized mindful eating practices, which focused on increasing
study participant’s awareness and ability to regulate hunger, food cravings, and eating
triggers. Mason et al. provided study participants with health information materials to

43
review at home. The study was successful. Study participants who practiced mindfulness
experienced greater reductions in food addiction symptoms and weight loss than control
participants (Mason et al., 2015). Additionally, Gearhardt et al. (2012) and colleagues
conducted a study on obese patients who were food addicted and found that food addicted
study participants struggled to lose weight because they struggled with elevated
depression, lower self-esteem, and inability to regulate their emotions. Finally,
Burmeister et al. (2013) found that participants lost a significant amount of weight after
seven weeks. However, those who showed higher food addiction scores (meaning that
they experienced more food addiction symptoms) lost a smaller percentage of their body
weight after seven weeks (Burmeister et al., 2013). This is because those who suffered
from food addiction had higher levels of binge eating, emotional eating, hedonic eating,
food cravings, and consumption of sugary foods compared to overweight and obese
participants without food addiction (Burmeister et al. 2013). In conclusion, these studies
lay a solid foundation for using social cognitive theory to address food addiction.
Rationale for the choice of this theory. Obesity and being overweight present a
complex problem for millions of individuals worldwide. With 53% of people who
attempt to lose weight failing to adhere to their diet plans, and one-third to one-half of
people regaining the weight, it is clear that there is more to weight loss than simply
dieting and exercising (Applehans, French, Pagoto, & Sherwood, 2016). Researchers
have discovered that there are neurological underpinnings involved in the weight loss
battle as well. In addition, researchers have found that food addiction plays a significant
role in obesity due to the role of the brain’s neurotransmitters and a person’s ability to

44
derive pleasurable feelings from food. According to researchers, there is a similarity
between those who suffer from obesity and those who suffer from drug addiction
(Gearhardt et al., 2012; Pepino, Stein, Eagon, & Klein, 2014). However, there is hope.
Healthcare professionals have used psychology and cognitive behavioral-based therapy to
treat addictions. Specifically, components of social cognitive theory have emerged as a
promising and successful way to treat various addictions. Healthcare professionals have
also used components of social cognitive theory, such as self-efficacy, in weight loss
treatment interventions with great success (McKee & Ntoumanis, 2014; Wilson et al.,
2015). However, to date, no researchers have applied components of social cognitive
theory to those who suffer from food addiction. This is the rationale for exploring food
addiction theory and social cognitive theory in this study.
How and why food addiction theory relates to the present study is that many
researchers have implicated food addiction in many studies as a significant contributing
factor to overeating, which leads to obesity and being overweight (Gucciardi, 2011;
Insawang et al., 2012; Lowndes et al., 2012). In addition, researchers have implicated
food addiction in studies of food cravings and excessive sugar intake (Gucciardi, 2011).
In addition, researchers have also linked highly palatable foods such as ice cream, cakes,
cookies, and various fast foods with the food additives MSG and HFCS Napoli (2008).
Those who are overweight and obese often consume these highly palatable foods, which
contribute to cravings, overeating, and obesity (Van Dillen & Andrade, 2016).
Although many researchers have reported a positive correlation between food
addiction, BMI, and highly palatable foods, very few have linked food addiction to foods

45
containing MSG and HFCS. The symptoms of food addiction, such as food cravings and
overeating, may be explained partially by the presence of the substances in these foods
that activate psychophysical response in the brain (Blaylock, 1999). Researchers have
found convincing support for food addiction theory based on studies demonstrating
neurological responses of people and animals when they are exposed to foods containing
MSG.
Additionally, although there are several studies of animal and human subjects
providing evidence that addictions and obesity can be treated with behavioral therapy
such as social cognitive theory, studies that explore applying social cognitive theory to
food addiction are lacking. Thus far, researchers have successfully demonstrated that
social cognitive theory can break addictive habits such as smoking cessation (Dickerson
et al., 2016), overeating (a symptom of food addiction), and poor food selection (an
additional symptom of food addiction). In the proposed study, I will provide meaningful
data and support as social cognitive theory -based health information is used to affect the
eating habits of overweight and obese women who suffer from food addiction.
The objective of this study is to determine if there is a significant difference in
food addiction among overweight and obese women who receive social cognitive theory-
based health information compared to overweight and obese women who receive non-
Social Cognitive based health information. The research question builds upon food
addiction theory and social cognitive theory by studying the differences in food addiction
between the group’s pre- and post-test, and define the differences between groups that

46
receive non- social cognitive theory-based health information and social cognitive theory
- based health information.
Conceptual Framework
The conceptual framework of the proposed study consists of two theories. The
first theory is Food Addiction Theory. The second theory is Social Cognitive Theory.
Combined, these theories will address and hopefully provide a potential solution to a
significant contributor to the obesity epidemic: food addiction. There is increasing
evidence that certain foods can stimulate the excessive release of the brain’s pleasure and
stimulating neurotransmitter–dopamine–which causes overeating, contributes to obesity,
and makes maintaining healthy food behaviors challenging. Meanwhile, components of
social cognitive theory have emerged as a viable approach for addressing various
addictions. When incorporated into weight loss studies, components of social cognitive
theory have increased and improved study goals and outcomes.
Key Statements and Definitions Inherent in the Framework
There are several key statements and definitions inherent in the framework. First,
researchers have shown that food addiction is a form of addiction that mimics drug
addiction in the brain. Therefore, in the context of the battle against obesity, managing
the symptoms of food addiction is not as simple as increasing a person’s willpower. The
second statement is that behavioral therapies such as social cognitive theory have been
shown to address symptoms of addiction and weight loss. Although to date no researchers
have applied social cognitive theory to addressing the symptoms of food addiction, in this
study, I will examine how food addiction will potentially be impacted when study

47
participants are exposed to health information that has been created based on components
of social cognitive theory.
Definitions Inherent in the Framework
Food addiction. Certain foods, whether seen or eaten, activates the same brain
circuitry that is activated by addictive drugs and thus regulates dietary behavior (Rogers,
2011).
Social cognitive theory. Social cognitive theory suggests that human behavior is
the product of a dynamic interplay between personal, behavioral, and environmental
influences that interact and are determinates of each other (Bandura, 1986; Glanz et al.,
2008).
How the Concept Has Been Applied and Articulated in Previous Research
The notion of previous research applying components of social cognitive theory
to food addiction is a new and fascinating concept. Although no researchers to date have
used components of social cognitive theory to treat food addiction, some have utilized
components of social cognitive theory to treat addiction, behavioral challenges, and to
promote positive weight loss. Heydari et al. (2014) applied components of social
cognitive theory to a group of individuals suffering from opium addiction. Heydari et al.
applied the self-efficacy component of social cognitive theory towards the design of an
intervention that focused on first creating a pre-condition of awareness that concentrated
on increasing awareness of the addiction process and health complications. They
followed this by educating study participants of the risks of their past behavior to their
health, as well as suggesting preventative approaches that they could utilize to overcome

48
urges to regress (Heydari et al., 2014). Finally, they used a component of social cognitive
theory by teaching problem-solving skills and how to positively engage another
component of social cognitive theory–external environment. Although Heydari et al.
(2014) articulated the components of social cognitive theory via regularly scheduled
meetings with former addicts, the approach and sequence taken are similar to the
approach that I took in the proposed study with the independent variable of social
cognitive theory -based health information. In addition, Heydari et al. indicated that
utilizing components of social cognitive theory in this manner and structure yields
successful results. Heydari et al. found that 90% of social cognitive theory -based study
participants quit their addition in comparison to the 73% of study participants in the
control group who quit their addiction.
In a food addiction study, Kenny (2013) found that obese rats would withstand
the pain of electric foot shocks to satisfy their food addiction, even when the
experimenter would provide a warning signal before applying the electric foot shock.
Humans who suffer from obesity-induced food addiction also experience similar
warnings from the body as their food addiction worsens. These warnings can range from
shocks of cardiovascular disease, diabetes, and reduced physical mobility as certain parts
of the body emit pain signals (Stienstra et al., 2014). Burmeister et al. (2013) stated that
although food addiction has been associated with binge eating disorder, bulimia nervosa,
and compulsive overeating, food addiction is a different construct and is distinct from
binge eating. Burmeister et al. (2013) also found that those who are food addicted did not
have greater beliefs that weight could be regulated through willpower alone. This is

49
important to this study because this reinforces and reiterates that more than willpower is
needed to fight obesity. This is also a significant reason for this study, as the food
addicted need more than willpower to reduce and eliminate the symptoms of food
addiction; applying a behavioral such as social cognitive theory might be ideal.
Finally, most researchers have used health information and education as a minor
component of weight loss and addiction studies. To date, researchers from only one study
appear to place a greater emphasis on the role of health information. Pierce et al. (2004)
utilized monthly newsletters to increase study participants’ self-efficacy to encourage
them to adopt healthier eating habits, which entailed increasing intake of fruits and
vegetables rich in micronutrients and phytochemicals. These newsletters focused on
providing study participants nutrition information, research updates, teaching self-
policing and monitoring to prevent undesirable food behavior, and provided motivation to
study participants to prevent relapse into old behavior patterns (Pierce et al., 2004;
Willard-Grace et al., 2015).
Literature Review
There are a multitude of studies related to the constructs of interest, which are
food addiction and components of social cognitive theory. However, to fully understand
the breadth and significance of food addiction, one must delve into obesity’s causes and
influences.
Obesity
As a result of the overconsumption of foods and insufficient energy expenditure,
some scientists have theorized that decreasing overall food intake to moderate levels

50
would prevent obesity and promote weight loss (Chaput, Klingenberg, Astrup, & Sjödin,
2011). In the effort to identify a potential solution to the obesity epidemic, it is important
to address obesity’s etiology. Obesity is defined as having a BMI over 30 kg/m, and
overweight is defined as having a BMI over 25 kg/m or a waist circumference over 35
inches or a body fat percentage over 32% (CDC, 2014; King, 2013; WebMD Inc., 2003).
BMI is commonly used in studies and I will take this approach in the proposed study as
well. Body fat percentage is infrequently used in studies, but still bears mentioning due to
its ability to calculate body fat accurately. Body fat percentage is commonly measured by
assessing the overall body composition using bioelectric impedance analysis, which
involves use of an electrical current to assess the total amount of water in the body
compared to muscle and fat (Oeffinger et al., 2014). An accurate body fat measurement is
contingent upon a precise height measurement (Oeffinger et al., 2014). For women,
obesity is defined as having a body fat percentage of 32% or higher (WebMD, 2003).
There are various scientific theories as to obesity’s causes. Some researchers
theorize that obesity can be influenced by genetics and family environment (King, 2013;
Lochrie et al., 2013). For example, one study conducted on twins that is used as the
cornerstone of obesity research found body weight to have a 70% chance of being
inherited along with waist circumference having a 65% chance of being inherited (Clark,
1956). The researchers found that body weight and waist circumference is one of the top
genetic factors that could be inherited (Barsh, Farooqi, O’Rahilly, 2000). Other
researchers studying Finnish twins found similar results; however, they also found that
obesity can be overcome with exercise (Silventoinen et al., 2009; Waalen, 2014).

51
Other scientists have speculated that obesity is due to the brain’s set point
malfunctioning (Greenway, 2015). Under normal circumstances, the body has certain
physiological mechanisms and systems in place to ensure the body maintains
homeostasis. For example, after food consumption, the mechanoreceptors in the stomach
and the hypothalamic paraventricular nucleus, ventromedial hypothalamus, and the
posterodorsal amygdala in the brain are activated (King, 2013). As the person continues
to consume food, the brain receives signals from receptors in the stomach, alerting the
brain that the stomach has reached or is reaching capacity, which in turn causes a
reduction in gastric emptying (King, 2013). Insulin levels are released in proportion to
the fat and sugar content of food consumed (King, 2013). The hormones ghrelin and
leptin are responsible for the appetite being stimulated or inhibited. The body then
indicates that it is full by emitting leptin. The process begins again when the person
experiences the sensation of hunger, which is caused by the stomach emitting the
appetite-stimulating hormone ghrelin (Miyazaki et al., 2013). This process is a significant
component of food addiction, because foods that contain HFCS change the body’s
process of feeling satiated by changing the body’s satiety signals. This is also important
because those who are obese or overweight, and people who identify as being addicted to
food, consume excessive levels of foods that contain HFCS, such as carbohydrates and
ice cream (Martin et al., 1995; Parylak et al., 2011).
In theory, this process should operate consistently, which is what proponents of
set point theory state. Scientists who are advocates of set point theory argue that the body
maintains a level of homeostasis by maintaining a certain weight, and will naturally

52
adjust if body weight increases or decreases outside of the normal range (King, 2013;
Swencionis & Rendell, 2012). However, this does not explain why obese people maintain
abnormally lower levels of ghrelin in their bloodstreams than their thinner counterparts
(Miyazaki et al., 2013). Also, obese people who have undergone bariatric surgery and
had part of their stomach removed have decreased levels of ghrelin production, yet in
clinical studies they still report experiencing feelings of significant hunger (Miyazaki et
al., 2013).
Externality theory states that the obese and overweight are unable to detect the
body’s internal cues indicating hunger and satiation (Stroebe, van Koningsbruggen,
Papies, & Aarts, 2013). Other researchers have found that the brain’s satiety centers in
obese people experience activation delays following consumption of certain foods and
highly palatable substances (Gibson, Carnell, Ochner, & Geliebter, 2010). Bragulat et al.
(2010) presented another reason for obesity and being overweight. They found that the
bilateral hippocampus/parahippocampal area of the brain experienced greater activation
in obese participants than in normal weight participants when exposed to food stimuli
(Bragulat et al. 2010). This means that obese and overweight people are particularly
vulnerable to high palatability foods because it makes eating very rewarding compared to
the experience of a person of normal weight (Barry et al., 2009; Bragulat et al., 2010).
Each theory has merit in discussions about obesity’s origins and reasons why
obesity persists. However, one fact remains absolute: being overweight or obese causes
significant health problems. These health problems can include hypertension, cancer, and
diabetes (Colombi & Wood, 2011; Persson, 2014). These health problems cause

53
individuals to suffer the financial burden of direct and indirect costs that have been
estimated to reach $147 billion (Center for Disease Control and Prevention, 2013). These
direct and indirect costs are attributed to the financial cost of obesity-related
pharmaceuticals, health care expenditures for diseases, and disabilities attributed to
obesity, such as coronary heart disease, hypertension, type 2 diabetes mellitus, and
certain types of cancer (Rappange, Brouwer, Hoogenveen, & Van Baal, 2009). Obese and
overweight individuals may also suffer from decreased workplace productivity due to
acute and chronic illness and absenteeism (Ulrich, 2005). For this reason, it is important
to discuss key contributors to the obesity epidemic, such as the food additives MSG and
HFCS.
Food Addiction
Recently, the theory of food addiction has been drawing national attention in the
news and scientific research. What makes food addiction so fascinating yet complex is
the body’s physiological response as well as the individual’s psychological motivation
(or lack thereof) behind food selection. The scenario is similar to what a person faces
when ingesting an illicit drug. A person is aware of the potential ill effects of consuming
an illicit drug, yet the person fails to possess motivation to not consume the illicit drug
(Barry et al., 2009). Food, however, is essential for life (Barry et al., 2009). How could
something so essential to life cause such a cascade effect in the body and lead to a loss of
control of behavior?
Several researchers have yielded evidence pertaining to the theory of food
addiction and how the brain’s neurological response to certain food is similar to the

54
brain’s neurological response when abusing drugs (Barry et al., 2009). For example,
Martin et al. (1995) indicated that obese women prefer carbohydrates such as cake and
doughnuts. In another study, Burmeister et al. (2013) discovered evidence of food
addiction undermining efforts to lose weight because the person is battling eating-related
and addiction pathologies, such as body shame and feelings of withdrawal.
Rolls (2011) contributed to food addiction research when he discovered that parts
of the brain, such as the primary taste cortex in the anterior insula and the adjoining
frontal operculum, contain neurons that detect the subtleties of viscosity, fat, texture,
temperature, and capsaicin in food. These areas of the brain are vulnerable to the
stimulating and addictive effects of processed foods such as cakes, cookies, and ice
cream. These foods often contain the addictive substances MSG and HFCS (Bellisle,
2008; Forshee, Storey, Allison, & Glinsmann et al., 2007). Continuous and repeated
exposure to foods containing harmful food additives such as MSG and HFCS can
predispose vulnerable individuals to eat compulsively (Barry et al., 2009; Zhang, von
Deneen, Tian, Gold, & Liu, 2011). This compulsive eating expresses itself as the person
makes poor food choices and exhibits poor ability to self-regulate behavior (Avena,
Bocarsly, Rada, Kim, & Hoebel, 2008).
Researchers have used the Yale Food Addiction Scale (YFAS) in food addiction
studies to monitor and evaluate excessive food consumption as well as other symptoms of
addiction. These symptoms of addiction include but are not limited to food cravings and
attending or avoiding certain events (Gearhardt, Corbin, and Brownell, 2009). This scale
also evaluates psychological distress, disordered eating, weight bias, and weight-focused

55
attitudes (Davis et al., 2011). For example, Meule and Kübler (2012) used this scale to
measure changes in the strength of cravings, and their results were used to support the
argument for food addiction as well as other symptoms of addiction, such as food
cravings and problem foods. Meule and Kübler (2012) found that the Yale Food
Addiction Scale allowed them to explore food cravings and excessive food consumption.
Their findings agreed with others’ that noted that individuals with addictive eating
patterns experienced more food cravings, yet simultaneously had no expectation of
positive reinforcement due to eating certain foods (Meule & Kübler, 2012).
There is evidence that points to similar neurological response between humans
and rats to foods and drugs (Zhang et al., 2011). For example, foods containing the
addictive substance MSG showed the primary taste cortex and ventral striatum to show
increased activity in MRI scans versus consuming those same foods that did not contain
MSG (McCabe & Rolls, 2007). In addition, McCabe and Rolls (2007) found correlations
for fullness and flavor in the parietal somatosensory operculum. Collison et al. (2010)
also found that study participants who were exposed to MSG consumed these foods in an
addicted-like fashion.
Biology of Food Addiction
Leptin and ghrelin levels. To understand food addiction, it is necessary to delve
into the physiological components that are the catalysts for the body’s physiological and
psychological responses. Undertaking this task also will allow one to gain further insight
into what is at stake when applying social cognitive theory to improve eating habits.
There are two regulators of appetite, cravings, and weight management: leptin and

56
ghrelin. These hormones are directly responsible for appetite stimulation; without it,
unbridled food consumption would take place (Darbandi et al., 2012).
Ghrelin is a hormone and neuropeptide (Stoyanova & le Feber, 2014) responsible
for appetite stimulation, weight gain, reward, mood, learning, and memory, by secreting
an activating growth hormone in the stomach and parts of the brain such as the pituitary
gland, hypothalamus, cortex, brain stem, and hippocampus (Costantini et al., 2011;
Stoyanova & le Feber, 2014). Absence or reduced level of ghrelin in the human body
results in decreased appetite (Fiszer et al., 2010). These reduced levels contribute to
obesity and being overweight by potentially over-stimulating appetite for those who are
vulnerable to the chemicals in HFCS and MSG.
There are two regulators of appetite, cravings, and weight management: leptin and
ghrelin. Leptin is a 167-amino-acid peptide hormone that is released from white
adipocytes, and reflect a person’s total body fat mass (Darbandi et al., 2012). It is
generated by brown fat tissue, the placenta, ovaries, skeletal muscle, the stomach,
mammary epithelial cells, bone marrow, the pituitary gland, and the liver (Darbandi, et
al., 2012).
Leptin and ghrelin also play significant roles in a person being overweight or
obese, and in food addiction (Barry et al., 2009). The greater the amount of body fat, the
higher the serum concentration of leptin (Darbandi et al., 2012). Increased levels of leptin
in the body result in the ability to suppress appetite and decrease fat stores (Darbandi et
al., 2012). To examine the association between obesity and leptin, Gibson et al. (2010)
conducted a clinical study and found that when exposed to a highly palatable food after a

57
24 hour fast, leptin-deficient obese rats experienced greater stimulation in areas of the
brain that engaged goal-directed behavior. In these cases, rats would be more motivated
to seek out a food reward after being exposed to a highly palatable food stimulus (Gibson
et al., 2010). For obese humans, some possess a genetic mutation that reduces the
production of the hormone leptin, thus preventing them from regulating their food intake
in response to increased body fat (Barry et al., 2009). This mutation also results in a
stronger-than-normal appetite, and feelings of a constant and gnawing hunger (Barry et
al., 2009). In this case, a person’s obesity is due to inaccurate hunger cues as the person
overeats not for pleasure, but because the ability to sense satiety is “broken” (Barry et al.,
2009)
High fructose corn syrup. One of the most significant factors that effects weight
gain and is a catalyst for obesity is excess food consumption, specifically foods
consumed that contain added sugars. The use of HFCS peaked in the American food
supply between 1970 and 2000 (Lowndes et al., 2012). The food industry began adding
HFCS to improve food palatability (Rolls, 2007). This is also because HFCS improves
the texture, flavor, and shelf-life of food, and prevents freezer burn (Tweed, 2008). It is
found in ketchup, pasta sauce, bread, cereal, salad dressing, yogurt, and frozen foods
(Johnson, Gower, & Gollub, 2009; Tweed, 2008). Although food palatability improved
since the adding HFCS in the 1970s, subsequent researchers revealed that consumption of
HFCS reduces the brain’s ability to detect leptin/satiety signals, resulting in metabolic
syndrome, overeating, and obesity (Gucciardi, 2011). The consumption of HFCS also

58
contributes to cravings, overeating, weight gain, and is addictive (Challem, 2014;
Collison et al., 2010; Gucciardi, 2011).
Since 1970, Gaby (2005) reported that HFCS consumption had exceeded the
consumption of any other food or food group. From 1970 to 1997, HFCS consumption
increased by 26% from 64 g/day to 81 g/day in 1997 (Gabby, 2005). In addition to
increased sugar consumption, the type of sugar used to sweeten food products such as
beverages, cakes, candy, cookies, bread, and salad dressings has changed (Gabby, 2005).
Due to greater cost savings for food manufacturers and increased food shelf life, the food
industry began to replace the sugar normally used in food products with HFCS in the
1970s (Gabby, 2005). By 1985, the use of HFCS had escalated to 26% use in total caloric
sweeteners consumed in the US (Gabby, 2005). Interestingly, studies indicate obesity
rates and HFCS consumption rise in lockstep with one another.
Two forms of HFCS are currently used in the nation’s food supply. HFCS-55 is
used to sweeten carbonated soft drinks and is 55% fructose and 45% glucose (Lowndes et
al., 2012). The second form of HFCS – HFCS 42, is used in baked goods and other
products and contains 42% fructose and 58% glucose (Lowndes et al., 2012). Studies
have shown that when the body ingests foods containing fructose versus glucose, the
body’s insulin, leptin, and ghrelin response are different (Lowndes et al., 2012). People
consume more calories when fructose is involved as opposed to glucose (Lowndes et al.,
2012).
There is accumulating evidence to indicate that HFCS is also a crucial causative
factor in obesity. In particular, researchers have linked HFCS to a myriad of metabolic

59
changes conducive to promoting obesity. Collison et al. (2010) suggested that diets
containing HFCS induce the expression of genes involved in carbohydrate and lipid
metabolism. The individuals also experienced negative effects on the expression of many
genes, which also includes several oxidoreductases such as arachidonate lipoxygenases,
and Cyp2b and Cyp2c members (Collison et al., 2010). In another study, Gaby (2005)
stated that HFCS has deleterious effects on one’s metabolism by reacting with protein
molecules to form toxic Advanced Glycation End-products (AGEs) which play a
devastating role in accelerating aging. In addition, HFCS consumption plays a role in the
pathogenesis of diabetes complications, cardiovascular disease, hypertriglyceridemia and
hyperuricemia, and for individuals who consume a hypercaloric diet, insulin resistance
(Gaby, 2005). Consuming other forms of sugar evokes the damaging cascade reaction of
releasing AGEs, but the reaction and volume of damaging AGEs are not at the same
amount as the level of HFCS (Gaby, 2006). Additionally, Collison et al. (2010)
discovered that HFCS’s damaging effects also cross the placenta to negatively affect a
developing fetus by inducing steatosis and mitochondrial disruption.
Although HFCS does little to benefit the human body and animals in clinical
studies, it benefits the food industry greatly (Forshee, Storey, Allison, Glinsmann, & et
al., 2007). To increase food sales, it is important to attract consumers by presenting foods
that present a certain color, aroma, freshness, and once ingested, a certain sweetness,
chewiness, texture, and humecancy (Barrett, Beaulieu, & Shewfelt, 2010). HFCS
accomplishes this. Moreover, this additive substance works on the same area of the brain
as morphine, nicotine, and alcohol (Napoli, 2008).

60
Monosodium glutamate. Several studies have linked similarities between food
intake patterns and food addiction as it pertains to the similarity between the body’s
physiological response to addictive illicit drugs (Napoli, 2008). The theory of food
addiction was formed based on several results from several researchers who have
uncovered that certain foods that contain MSG and HFCS affect the body’s neurologic
pathway in the same way as the brain of someone that abuses drugs (Napoli, 2008).
Studies by Insawang et al. (2012) and Ren et al. (2011) indicated that MSG consumption
has been linked to high blood pressure, obesity, type II diabetes, metabolic syndrome,
and an increase in body mass, regardless of food intake. In addition, Ren et al. further
examined the topic and found that previous researchers claimed that MSG induces
obesity by elevating plasma glutamate levels in the brain to toxic levels, which in turn
affects the body’s energy homeostasis levels. In animal tests, exposure to MSG resulted
in elevated triglycerides, and increased fasting glucose and insulin levels, which are all
indicators of metabolic disorder markers (Insawang et al., 2012). Interestingly, Ren et al.
studied the effects of MSG in food preferences with animals, and found that animals had
strong preferences for MSG, especially if a low-fat food contained MSG. Insawang et al.
(2012) confirmed previous research by finding a correlation between consuming MSG,
metabolic syndrome, and being overweight in rural Thai populations. He et al. (2008)
confirmed this finding examining the relationship between MSG intake and obesity
among obese participants; however, a limitation of this study was that the obese
comprised only 3% of the study. Nevertheless, there was a partial correlation between

61
MSG intake and obesity (He et al., 2008). The lack of a large sample of He et al. (2008)
study presents a gap in existing research.
Monosodium glutamate’s contribution to obesity. Researchers frequently
discuss food addiction and its role towards the obesity epidemic (Davis et al., 2011;
Hardman et al., 2015). According to those that either self-identified as a food addict or
were identified by scores from the Yale Food Addiction Scale (see Appendix A), the
foods that were often listed as contributors to food addiction include processed food such
as cakes, candies, and fast food (Martin et al., 1995). Various researchers have noted
these foods as being infused with the addictive food additives MSG and HFCS (Barry et
al., 2009; Lowndes et al., 2012; Lenz, 2007). However, no researchers have yet to
examine this more closely. In this section, I will expound upon MSG and its contribution
to the obesity epidemic and food addiction.
Monosodium glutamate is an excitotoxin that functions by improving food flavor
(Blaylock, 1999). It is present in prepared foods such as soups, chips, fast foods, frozen
foods, and canned goods (often disguised in food labels under alternative names such as
hydrolyzed vegetable protein, vegetable protein, natural flavorings, and spices). MSG
impacts the brain by damaging neurons and exciting these cells to death (Barry et al.,
2009; Blaylock, 1999). As more cells perish, the ability to derive pleasure from
consumed food diminishes, resulting in the need to consume more food, which in turn
results in overeating. The biological effect is similar to what is experienced by drug
addicts when they attempt to get high. Drug addicts not only need to consume more of
the drug to achieve the same high, but also crave the drug (Martinotti et al., 2017). This

62
craving is one of the reasons why both drug addicts as well as the obese relapse and
consume the addictive substance (Barry et al., 2009).
Neurological impact. As previously mentioned, considerable evidence has been
mounting that demonstrates that food addiction and drug addiction share comparable
neurobiological pathways, such as the opiate and dopamine reward circuitries (Barry et
al., 2009; Val-Laillet et al., 2011). Dopamine is the brain’s reward system; steadily
increasing its rate of release and thus and the body’s perception of increasing rewards can
also be associated with food addiction as one consumes foods that contain MSG and
HFCS (Zhang et al., 2011). Brain scans of people with food addiction have shown low
levels of striatal dopamine (DA) D2 receptors and a high prevalence of A1 allele (Zhang
et al., 2011). Because of this condition, overeating serves to raise low DA levels and
serves as a form of positive reinforcement (Zhang et al., 2011).
Driscoll (1994) wrote an article that concurs with this current study and discussed
the struggles of those that suffer from food addiction. Driscoll discussed that avoiding
certain “trigger foods” is not a matter of willpower. People suffering from food addiction
are unable to discern portion sizes. For example, a cow looks like a four-ounce steak to
someone that suffers from food addiction. Driscoll also discussed that food addicts
experience cravings, a form of body dysmorphic disorder in which food addicts see
themselves as smaller than they are (Driscoll, 1994). The author suggested that the
solution to food addiction is to measure and control one’s portion sizes (Driscoll, 1994).
However, the author may have inadvertently mentioned the limitation to this solution.
Driscoll stated that a person with food addiction is obsessed with food, and that once the

63
person begins consuming certain foods, that a “feeding frenzy” is initiated and that the
person cannot stop eating. This “feeding frenzy” is what leads to overeating. Driscoll also
stated that food addicts constantly and obsessively think about food. This discovery
would support and possibly explain the role of ghrelin in appetite homeostasis. In
addition to regulating appetite by prompting the body to consume more food when it feels
it is hungry, ghrelin also plays a role in cognitive functions such as memory (Costantini et
al., 2011). This biological process could explain why a food addict craves not only
certain foods, but also becomes obsessed with certain foods. Foods that contain MSG and
HFCS modify the brain’s circuitry by changing how these foods are perceived when
eaten (mouth feel, texture, and freshness) as well as the pleasure that is perceived when
eaten (Barrett et al., 2010)
Joranby et al. (2005) conducted a review that elaborated on the psychobiological
processes that trigger hunger, and also assessed the link between addiction, overeating,
and obesity, and how it impacts the brain. They found evidence from previous studies
that utilized functional brain imaging. These researchers yielded results indicating that
the brain experiences changes similar to reactions produced by consumption of illicit
drugs when a person overeats and becomes obese (Joranby et al., 2005). They also found
evidence that drug abusers and those who suffer from eating disorders and are obese are
biologically vulnerable. This vulnerability could make them more susceptible to loss of
control, impulsiveness, and emotional and environmental cues (Joranby et al., 2005).
Psychological evidence of food addiction. Martin et al. (1995) and Fortuna
(2012) reported that obese people consume more foods such as sweets, fats, and

64
chocolates than their normal-weight counterparts. Withdrawal symptoms abound in the
form of headaches, nausea, fatigue, and irritability (Bocarsly, 2016) when the obese
attempt to curb consumption of fattening foods, making dieting difficult. To relieve these
temporary discomforts, the obese return to their old eating habits (Bocarsly, 2016).
Perhaps if the obese and overweight knew that the discomfort that they experienced is
temporary, they would continue to positively modify their food intake instead of
returning to their original eating regimen (“Can you conquer,”2014).
Ludman et al. (2010) indicated that personality changes are correlated with
obesity. Some have also found depression and changes in brain matter such as reduction
of inhibitions (Goossens, Braet, Van Vlierberghe, & Mels, 2009; Val-Laillet et al., 2011).
In another study, (McCann, 2011) found weight to be associated degrees of extroversion,
neuroticism, higher agreeableness, and lower openness to experience. Meanwhile, obese
individuals exercised less than non-obese individuals and consumed less healthy foods
(Brook, Lee, Finch, Balka, & Brook, 2013). Moreover, obese people experience
decreased levels of satisfaction with life when compared to their non-obese counterparts.
This decreased level of satisfaction can impact many facets of life, including mate
selection and social relationships (Brook et al., 2013).
Food addiction and social cognitive theory relate to this study’s approach and
research questions in several ways. Food addiction theory addresses the reason why over
half of Americans are both overweight and obese (CDC, 2013). As previously stated,
those who suffer from food addiction overeat despite the brain registering little or no
external reward (Wright, 2011), leading to excess calories consumed, which in turn leads

65
to being overweight or obese. Parylak et al. (2011) observed that carbohydrates and fast
food tend to be some of the most heavily abused food groups among those who suffer
from food addiction. Numerous researchers have confirmed that these foods are sources
of MSG and HFCS (Collison et al., 2010). MSG and HFCS have also been implicated in
studies as a catalyst to food addiction (Barry et al., 2009; Collison, et al., 2010).
Food addiction theory also relates to instrument development and data analysis.
The theory is applicable because I measured the differences in food addiction levels and
symptoms when components of social cognitive theory were applied to health
information that was shared with one group of overweight and obese women while non-
social cognitive theory-based health information was shared with the second group. I
measured food addiction using the Yale Food Addiction Scale. This instrument was
created because professionals working in addiction and nutrition fields observed
symptoms of food addiction (Gearhardt et al., 2009). Gearhardt et al. (2009) found that
although there was evidence of the physiological components of food addiction (in the
form of stimulation of the pleasure centers of the brain), the psychological sides of food
addiction had not been explored. The Yale Food Addiction Scale examines the
psychological element by examining the behavioral indicators and symptoms of
dependence (Gearhardt et al., 2009).
Social Cognitive Theory and Weight Loss
Additional researchers have also noted the role of the cognitive process associated
with food choices and health outcomes (Burns & Rothman, 2015; Wethington, 2005).
Some have explored social cognitive theory along with various health and eating

66
behaviors (Nollen et al., 2008). Founded by Bandura, social cognitive theory was derived
from previous theories designed by Miller, Dollard, and Rottler (Glanz et al., 2008).
Originally known as Social Learning Theory, social cognitive theory was based on and
acknowledged the complexity and capacity of the human mind to process information
(Bandura, 1986; Glanz et al., 2008). Social cognitive theory is also based on the
influential biases that play a pivotal role in behaviors that are gained through
observations, experiences, and communication (Bandura, 1986; Glanz et al., 2008).
Social cognitive theory is based on reciprocity, in the form of interactions that are guided
by a person and his or her environment (Anderson, Wojcik, Winett, & Williams, 2006;
Bandura, 1986; Glanz et al., 2008). Bandura (1986) stated that each factor - a person’s
behavior, cognitive capability, personal factors, and environment - work together to
influence interact, determine, and therefore reciprocate between one another. Thus, many
people have the ability to create and construct their environment for their own purposes
and desires (Glanz et al., 2008). According to Bandura (1986), advanced cognitive
capability coupled with flexibility enables one to create ideas transcending one’s sensory
experiences and belief in one’s ability to achieve or reach goals. Bandura (1986) also
believed that forethought plays a pivotal role in motivation. Social cognitive theory is
based on nine key concepts:
1. Reciprocal determination−Environmental influences on a person’s behavior;
2. Outcome expectations−A person’s beliefs about the consequences of their
choices and actions;

67
3. Self-efficacy−Belief in one’s ability to execute necessary behavior for desired
goal;
4. Collective efficacy−Beliefs about the ability of the group to execute necessary
behaviors for desired goal;
5. Observational learning−Learning new behavior via direct experience through
peer modeling;
6. Incentive motivation−Using punishment or praise to modify behavior;
7. Facilitation–Possessing the tools to accomplish certain goals easier;
8. Self-regulation–Controlling oneself by monitoring one’s actions and utilizing
various means to do so such as goal setting, rewarding oneself, and social;
9. Moral disengagement – Disengaging self-regulating moral standards by
dehumanizing people (Bandura 1986; Glanz et al., 2008).
Social Cognitive Theory is based on and acknowledges the complexity and
capacity of the human mind to process information, and the influential biases that play a
pivotal role in behaviors that are gained through observations, experiences, and
communication (Bandura, 1986; Glanz et al., 2008). Social cognitive theory is based on
reciprocity, in the form of interactions guided by individuals between their environments
(Anderson et al., 2006; Bandura, 1986; Glanz et al., 2008). The theory explains that
people have the ability to determine their environment for their purposes (Glanz et al.,
2008). According to Bandura (1986), advanced cognitive capability coupled with
flexibility enables one to create ideas transcending one’s sensory experiences. Bandura

68
also believed that forethought and self-efficacy play a pivotal role in motivation. Because
I explored the construct of self-efficacy in this study, I will expound more on this topic.
According to Ozer and Bandura (1990), individual self-efficacy refers to a
person’s perceptions of their ability and capability to garner enough motivation, cognitive
resources, and action steps to exert control over certain events. Self-efficacy pertains to
what a person perceives they can do with the resources they have to impact and control
events in their life and environment (Bandura, 2007). An individual’s self-efficacy and
his/her ability to act upon self-efficacy in certain situations determines the level of
interaction and engagement a person may have with his or her environment (Ozer &
Bandura, 1990). Self-efficacy is developed by individual past life experiences, and those
experiences shape and form people’s beliefs about their ability to produce the desired
outcomes (Bandura, Barbaranelli, Caprara, & Pastorelli, 2001). It is a vital element to
social cognitive theory because it affects
adaptation and change not only in their right but through their impact on other
determinants. Such beliefs influence aspirations and strength of commitments to
them, the quality of analytic and strategic thinking, level of motivation and
perseverance in the face of difficulties and setbacks, resilience to adversity, causal
attributions for successes and failures, and vulnerability to stress and depression
(Bandura et al., 2001, p. 187).
The amount of self-efficacy that one has regulates many things. It regulates one’s
perceived capacity to exercise control of not only one’s actions in a stressful situation,
but one’s thoughts as well (Ozer & Bandura, 1990). This ability can be particularly vital

69
in behavioral and lifestyle changes, such as adopting healthier eating habits by avoiding
certain foods or choosing a healthier alternative. Ozer and Bandura (1009) have also
attributed self-efficacy to the anxiety and stress that one experiences when faced with
challenging situations that threaten to derail previously successful attempts at adopting
new behaviors. Finally, Bandura and Locke (2003) have attributed self-efficacy to the
motivation and levels of performance that dictates behavior.
In clinical studies, self-efficacy has been identified as both directly and indirectly
playing a critical role in addiction and adopting healthier behaviors. Lower levels and
doubts about one’s self-efficacy resulted in decreased or discontinued adherence to the
new behavior (subsequently ignoring the problem), and higher levels of self-efficacy led
to increased adherence to the behavior (Bandura, 2005). In a separate clinical study,
Bandura (2007) found low self-efficacy to result in an inability to manage negative
emotions such as stress, depression, loneliness, and social pressures to engage in abuse of
addictive substances such as alcohol. In another study, Nollen et al. (2008) noted self-
efficacy as a factor in exercise, dietary interventions and fruit and vegetable consumption
among low-income populations.
Social cognitive theory also suggests that human behavior is the product of a
dynamic interplay between personal, behavioral, and environmental influences that
interact and are determinates of each other (Bandura, 1986; Glanz et al., 2008). Past
researchers have demonstrated that social cognitive theory has been effective in
impacting weight loss. Nollen et al. (2008) found that applying social cognitive theory
helped study participants lose weight by reducing their consumption of prepared and

70
processed foods. They also reviewed important facets of social cognitive theory, such as
self-efficacy and psychosocial influencers on body composition (Nollen et al., 2008). The
gap in the research as it pertains to this study is that Nollen et al. (2008) focused on
reducing the consumption of prepared and packaged foods. However, they did not
monitor nor acknowledge the role of high fructose corn syrup and monosodium glutamate
in prepared and prepackaged foods (Blaylock, 1999).
Additional researchers have demonstrated that social cognitive theory can be used
to aid in weight loss. For instance, Nollen et al. (2008) found study participants who
utilized facets of social cognitive theory, such as self-efficacy, for weight loss
successfully lost weight. Basen-Engquist et al. (2013) found that cancer survivors lost
weight by focusing on their self-efficacy (a construct of social cognitive theory) by
remaining positive and focusing on the beneficial outcome of exercise. They further
revealed that participants increased the amount of time spent exercising due to
experiencing an increase in their levels of self-efficacy (Basen-Engquist et al., 2013).
Researchers have also suggested that social cognitive theory weight loss-based therapies
are successful because they focus on crucial areas such as self-efficacy, but could be
improved if self-efficacy was focused on in “real time” instead via weekly meetings
(Basen-Engquist et al., 2013).
Other researchers have shown that self-efficacy plays a significant role in food
choices and decision-making. The amount of self-efficacy a person has is important to
dietary success. Researchers have suggested that those who are trying to lose weight who
have a low sense of self-efficacy do not successfully lose weight or make beneficial

71
lifestyle choices that would improve health, such as changing food choices or starting and
maintaining an exercise program (Bandura, 2007). When obese individuals with high
self-efficacy endeavor to improve their health behavior, they are more successful than
individuals with low self-efficacy.
Social Cognitive Theory applies to this study’s approach and research questions
in the following ways: First, social cognitive theory is a psychological theory with
constructs designed to facilitate behavioral change. One element of social cognitive
theory entails modifying of a person’s attitude towards certain goals or challenges in
order to facilitate behavioral change. Bandura (1969) stated that exposure to persuasive
communications that challenge people’s attitudes about certain beliefs causes cognitive
disequilibrium. He also stated that people can be persuaded to “change their evaluations
of an attitude object by presenting them with new information about its characteristics”
(Bandura, 1969, p. 599). It is my hope that the social cognitive theory-based health
information (new information) will help study participants change their attitudes about
food addiction symptoms and consuming certain foods. If this successful, then there
should be a change in the Yale Food Addiction Scores once I resurvey participants,
which would impact the data.
Second, social cognitive theory applies to this study and research questions by
helping those who suffer from food addiction to manage their symptoms. When applied
to customize the message and wording of health information presentations, I anticipated
that participants will not only have the tools to manage the symptoms of food addiction,
but be more successful in managing these symptoms than a group receiving a non- social

72
cognitive theory-based health information. One of the reasons this has such enormous
potential is its components. Social cognitive theory addresses both internal and external
factors involved in behavioral change. For example, social cognitive theory has an
observational learning component that states that a new or desired behavior can be
learned by observation (in person or via media) of the desired behavior and its
consequences (Bandura, 1969; Glanz et al., 2008). This has the potential to affect internal
motivation for example via self-efficacy–the capacity to believe that one has the ability to
complete a challenging task (Bandura, 1969; Glanz et al., 2008) as well as external
motivation.
Previous researchers have explored the impact of modifying human behavior,
food consumption, and exercise patterns by providing health information that taps into
facets of human nature that are influenced by components of social cognitive theory, such
as self-efficacy and outcome expectations. However, no researchers have explored
reducing food addiction symptoms by providing health information via an electronic
presentation with wording based on the constructs of social cognitive theory. For
example, Basen-Engquist et al. (2013) explored self-efficacy along with exercise, but did
not explore the differences between exercise and consumption of foods that contain MSG
and HFCS. Kemps, Tiggemann, and Griggs (2008) found that food cravings−a
symptomology of food addiction−are responsible for failed diets and feelings of
depression and shame, but did not specifically measure foods consumed.

73
Ways Researchers Have Approached the Problem
Over the years, food addiction has been a hotly-debated and explored topic among
researchers. Researchers have investigated various facets of food addiction, ranging from
the validity of food addiction to its usefulness. Because food addiction is still a young
area of research, there are a limited amount of studies that explore addressing the
problem of food addiction. To date, only a handful of researchers have approached and
attributed the problem of food addiction and being overweight or obese to food addiction
directly.
Pepino et al. (2014) approached reducing and eliminating food addiction by
conducting a longitudinal study of bariatric patients. This method yielded great success
because 93% of food-addicted study participants who underwent bariatric surgery
experienced a remission of food addiction (Pepino et al., 2014). However, Pepino et al.’s
(2014) weakness was that there was a chance of the results of the study being influenced
by dietary counseling that was provided after study participants underwent bariatric
surgery.
In another study on food addiction, Burmeister et al. (2013) researchers attempted
to address food addiction by implementing a behaviorally-based weight loss intervention
for overweight and obese adults. Their study was successful in the fact that food-addicted
study participants did lose weight, although Burmeister et al. stated that one weakness
was those with food addictions lost less weight than study participants who were not
diagnosed with food addiction, as measured by the Yale Food Addiction Scale. The
weakness in Burmeister et al.’s study was the inability to apply the study results to a

74
more diverse population because the sample consisted of predominately Caucasian
females.
Lent, Eichen, Goldbacher, Wadden, and Foster (2014) examined food addiction in
a large sample of obese individuals with type two diabetes who were willing to
participate in a behavioral weight loss intervention for six months. Lent et al. (2014)
found similar results to Burnmeister et al. (2012) in that although food-addicted
participants lost weight, they lost less weight than their non-food-addicted study
counterparts. In addition, one of the strengths of Lent et al.’s study in comparison to
Burnmeister et al.’s was the diversity of the study participants of Lent et al.’s. Lent et al.
included more African Americans (59%), versus Burnmeister et al. who included mostly
Caucasian participants (84.2%). Lent et al. stated that one of the potential weaknesses of
their study was the short duration, and that study participants were selected because of
their medical condition (diabetes), or that they were emotional eaters. Therefore, these
afflictions may not be generalizable to the broader obese population.
Researchers have approached utilizing components of social cognitive theory for
weight loss and handling addictions in various ways. Heydari et al. (2014) approached
utilizing components of social cognitive theory in an educational program to eliminate
study participant’s addiction to opium. This approach yielded great success because it
was based on each part of the social cognitive theory model in sequence. Ninety percent
of study participants experienced elimination of their addiction (Heydari et al., 2014).
Heydari et al. (2014) did experience a minor weakness in their study. Study participants
with low self-efficacy at the start of the study did not attempt to quit their addiction

75
(Heydari et al., 2014). Zheng et al. (2007) addressed smoking addiction in their study
while utilizing components of social cognitive theory in five health education training
sessions over the course of three weeks on a population of 118 smokers. The study was
successful. Forty percent of study participants in the social cognitive theory-based health
education group quit smoking compared to 5% of the control group. Zheng et al. (2007)
stated that one potential weakness of their study was the social and cultural climate of the
country regarding to smoking compared to other countries. In China, smoking is socially
perceived as a personal decision. In addition, tobacco control policies and public health
messages in China are not as visible and widespread compared to other countries.
Therefore, a health education study with an anti-smoking message would be a novelty
and unique to study participants as opposed to being easier to ignore because of repeated
exposure to anti-smoking messages if study participants were in another country (Zheng
et al., 2007).
Rationale for Selection of the Variables
For quite some time, weight loss experts, as well as the general public, upheld that
the key to weight loss was a simple equation of “calories in and calories out” (Schwenk,
2014). This school of thought eluded to the notion that if individuals wanted to lose
weight, all they had to do was make sure to eat fewer calories than they burned. Although
this outlook still pervades certain scientific journals and publications, in more recent
studies, researchers are illuminating a different reason as to why millions of Americans
are not losing weight. By taking a more sophisticated approach to examining how the
body metabolizes food and how the brain responds to certain food groups, additional

76
research has emerged that demonstrates that there are outside influences that affect food
choices. Researchers are beginning to come to the realization that managing one’s weight
is not merely a matter of willpower and self-control.
The rationale for selection of food addiction and social cognitive theory entails
the following reasons: The first is that although numerous studies have been conducted to
examine ways to manage and eliminate obesity, it is the opinion of this researcher that it
is important to acknowledge the role of biology and how certain foods can influence
eating behavior. Food addiction only addresses the biological and behavioral factors of
eating behavior. The second rationale for the selection of food addiction and social
cognitive theory is that researchers have successfully used social cognitive theory to
reduce and eliminate addictive behavior. One of the reasons for social cognitive theory’s
success in studies is because it addresses all facets of addiction, behavioral change, and
reciprocation. This reciprocation takes place between individuals, their external
environment, and their outcome expectations for their set goals. The final reason and
rationale for the selection of food addiction and social cognitive theory is that although
researchers have conducted promising research on these variables separately, no studies
have been performed on these variables together.
What Is Known, What Is Controversial, and What Remains to Be Studied
Two issues are controversial to researchers and appear to evoke mixed reactions.
The first and most pertinent issue to this researcher is that one of the premises of food
addiction is that it rests on the idea that it is fostered by high fat and high sugar foods.
However, this researcher feels that these categories are too broad. Ziauddeen and Fletcher

77
(2013), concurred and made the same observation. According to Ziauddeen and Fletcher,
the current food addiction model has not explored beyond the idea of foods that contain a
high amount of fat and sugar. Ziauddeen and Fletcher recommended that researchers
narrow the category by exploring components of these foods, such as concentration of
nutrients in these food items that may perhaps stand as a catalyst to the addictive process.
Ziauddeen and Fletcher further expounded upon this line of thinking by likening this
situation to something that food addiction has often been compared to–drug addiction.
They stated that just as drugs vary in their potency and addicting potential, foods could
vary as well. Ziauddeen and Fletcher argued that addicting foods should be narrowed
down and delineated to identify what drives the addition. Is there a common substance?
Is this an addictive substance? This outlook remains to be studied.
Fortunately, researchers outside of the specialty of food addiction are already
pursuing this path. Blaylock (1996), Meule and Kübler (2012), and Napoli (2008) have
all found that highly processed food such as those containing high fat and sugar contents
show signs of containing MSG and HFCS, and that these chemical additives have been
linked to food addiction. Perhaps in time, researchers from these two specialty areas will
collaborate and take the next step in food addiction research.
Ziauddeen and Fletcher (2013) mention a second issue of interest and controversy
regarding food addiction. They questioned the validity of the food addiction model in the
context of those who are obese and suffer from binge eating disorder. Their justification
is that binge eating disorder is an entirely different psychological profile that compels a
person to participate in disordered and compulsive eating (Ziauddeen & Fletcher, 2013).

78
The person continues this behavior despite negative consequences, and makes a
significant effort in acquiring the addictive substance (Ziauddeen & Fletcher, 2013).
However, food is needed to live. Furthermore, most do not need to exert significant effort
to acquire food.
One key point that remains to be studied is the concept of shared genetic
susceptibilities (Ziauddeen & Fletcher, 2013). Researchers have identified that obese
people, just as with drug addiction, are physically vulnerable due to a lower reward
threshold (Comings & Blum, 2000). Researchers conducting studies on families have
linked drug addiction to alcoholism, and this, in turn, is associated with an increased risk
of obesity (Dinwiddie & Cloninger, 1991). In both of these scenarios, these people are
vulnerable to the food that activates hedonistic sides of the brain (high fat and high sugar
foods) and therefore more prone to food addiction.
Summary and Conclusions
The major themes in the literature entail the following: First, food addiction and
the overeating that takes place with people who suffer from this affliction share a
commonality and similarity to drug addiction. Based on this evidence, food addiction
could be one of the leading reasons why people who attempt diets subsequently fail. As
soon as food-addicted individuals use their willpower and diet to improve their health,
they are battling dopamine–the brain’s neurological signal of pleasure that urges the
person to overindulge regardless of the consequences–a similar battle that drug addicts
experience when they try to resist the urge to consume drugs.

79
To combat addiction and obesity, health industry professionals continue to utilize
behavior therapies. Researchers have identified components of social cognitive theory as
potential leaders and effective tools in addressing symptoms of addiction and treating
weight loss. In this chapter, I discussed various studies in which components of social
cognitive theory have been utilized successfully.
There are several key items that are known in the discipline related to this topic.
First, researchers now know that food addiction is real addiction–a unique addiction–but
a real addiction nevertheless. Second, researchers now understand how food addiction
affects the brain and how it contributes to overeating, leading to addiction. Third,
although researchers have indicated that food addiction has been linked to highly
palatable foods, there are a few things that are not known in the discipline that are related
to this topic. For example, although researchers indicate that food addiction has been
linked to highly palatable foods, there is a limited number of studies linking food
additives such as MSG) and HFCS to food addiction. Also, although there are compelling
studies linking food addiction symptoms to MSG and HFCS, these are few. Furthermore,
although researchers have demonstrated the effectiveness of social cognitive theory in
reducing/eliminating addiction symptoms, improving weight loss outcomes, increasing
healthy eating outcomes, and reducing/eliminating symptoms commonly associated with
food addiction, no study to date has directly applied components of social cognitive
theory to food addiction.
However, this lack provides an opportunity for the proposed study. This study
will fill at least one of the gaps in the literature, and will extend knowledge in the

80
discipline by measuring changes in food addiction levels and symptoms between groups
of overweight and obese women as measured by the Yale Food Addiction Scale. I will
expose one group of participants to health information based on components of social
cognitive theory while the other group will receive basic health information. In chapter 3,
I discuss the methodology, setting, sampling, instrumentation, and analysis used in the
study.

81
Chapter 3: Research Method
The purpose of this study was to examine the influence of health information
based on social cognitive theory on food addiction among obese and overweight women.
In Chapter 3 I discuss research methods used in this study, including the research design,
sampling, instrumentation, data analysis procedures, and ethical considerations. I also
discuss the rationale for the research design; sample selection, characteristics, and size;
and the instruments used (surveys and questionnaires). I conclude the chapter by
describing the data collection and analysis processes.
Research Design and Rationale
Researchers have shown that food addiction is correlated to higher BMI (Meule,
Papies, & Kübler, 2012); therefore, I selected overweight and obese women for this
study. I chose women for this study because researchers indicated that women have a
higher interest in their body image and are more motivated to lose weight than men
(Meule et al., 2012). Because women have a higher interest in their body image and are
more motivated to lose weight than men, study participants may have been more
motivated to adhere to health information based on social cognitive theory. Increased
motivation may have reduced the incidence of participant attrition over the course of the
study’s 4-week period (see Niazi, Adil, & Malik, 2013).
For this study, I identified participants as candidates according to their BMI
calculated by using the CDC equation, which involved dividing a subject’s weight in
kilograms over the subject’s height squared in centimeters (CDC, 2015). I classified
potential study participants as overweight (25-29.99 kg/m) or obese (>30 kg/m2) using

82
the cut-off points listed by CDC (2015). The justification for including potential
participants was that they were old enough to provide informed consent. I assumed that
potential participants would possess the necessary reading comprehension level to
complete the questionnaires and instruments, and that they would be a diverse population
consisting of various ethnic backgrounds and ages.
I used a quantitative, quasi-experimental approach. This method is used when
researchers develop a hypothesis or theory that states that a difference in a dependent
variable is affected or changed due to a manipulated independent variable when
compared between two or more groups (Green & Salkind, 2011). The purpose of this
study was to examine how components of Bandura’s social cognitive theory, when
applied to health information, may affect food addiction level. The quantitative approach
was appropriate because it enabled me to test the numerical changes in the dependent
variable between two groups (see Pallant, 2016). I sought to examine the differences in
food addiction between two groups of overweight and obese women in which one group
received health information based on social cognitive theory and the other group received
health information not based on social cognitive theory.
The research design for this study was between subjects over the course of 4
weeks. Using a pretest, I measured differences between the two groups of female
overweight and obese study participants. I e-mailed the first group of study participants a
PowerPoint presentation containing health information based on social cognitive theory.
Both groups of participants received the Unites States Department of Agriculture Food
Pyramid to ensure that participants in both groups would receive standardized nutrition

83
information. The Food Pyramid supported the health information featured in the
presentations. I conducted a repeated-measures ANCOVA to examine participant scores
from the Yale Food Addiction Scale. Using the ANCOVA, I compared pretest and
posttest differences between the groups (see Mara et al., 2012). This approach allowed
me to use the pretest as a covariate, which increased the power of this quasi-experimental
study in determining whether the health information played a role in anticipated changes
in food addiction scores. I used SPSS 25.0 to analyze the data.
The study variables included the following: The independent variable was group
status: either receiving health information based on social cognitive theory (Group 1) or
not based on social cognitive theory (Group 2). Group 1 received weekly presentations
that included health information modeled using key elements of social cognitive theory,
such as self-efficacy, outcome expectations, observational learning, incentive motivation,
facilitation, and self-regulation. Group 2 received weekly presentations that disseminated
health information that was not modeled using social cognitive theory.
The health information based on social cognitive theory (Appendix C) was
designed to increase participant knowledge of healthy eating and food addiction, which
included the effects of eating foods that studies have shown foster food addiction (i.e.,
foods that contain the food additives MSG and HFCS). Group 2 received a similar
presentation weekly, but the presentation’s message was not based on social cognitive
theory. The health information was devoid of social cognitive theory elements such as
self-efficacy, outcome expectations, observational learning, incentive motivation,
facilitation, and self-regulation (Appendix D).

84
Two research design elements pertained to the design choice. The first constraint
was time. I scheduled the study to be conducted over 4 weeks to reduce the chances of
participant attrition. The second constraint was financial. Because this study was not
funded by any organization, there were financial limitations that prevented me from
offering additional cash incentives to study participants.
This design choice was consistent with research designs needed to advance
knowledge in the discipline in two ways: First, previous researchers who examined the
differences and changes between groups at two points of time chose an ANCOVA. For
example, Hintz, Frazier, and Meredith (2015) selected this approach when they explored
the effectiveness of an online intervention based on self-efficacy, a component of social
cognitive theory, to help college students deal with stress more effectively. To determine
whether the posttest scores increased because of the online intervention, Hintz et al.
(2015) used a pretest as a covariant during the ANCOVA analysis. In another study,
Dijkstra and Bos (2015) compared changes between groups of smokers exposed to new
graphic cigarette warning labels. Gulliver et al. (2016) used a repeated-measures
ANCOVA to test their hypothesis that one group of firefighters participating in a
behavioral change intervention delivered face-to-face would show significantly more
successful results compared to the second group of firefighters participating in a
behavioral change intervention delivered via video.
Methodology
For this study, I recruited participants from a private school in Chicago, IL, the
Walden University online participation pool, Findparticipants.com, and

85
Researchandme.com. Selection criteria included the following: (a) female, (b) at least 18
years of age, (c) BMI over 25, (d) overweight or obese, and (e) not currently pregnant or
not have given birth in the last 6 months. I calculated the participants’ BMI based on self-
reported height and weight that participants submitted when they completed the e-mailed
survey that accompanied the pretest and posttest. All ethnic and cultural backgrounds
were eligible to participate; participants who did not fit the inclusion criteria were
excluded from the study. However, they were provided the health information. As a
contingency plan to ensure that I secured the minimum number of participants (68) for
my study, snowball sampling and chain-referral sampling were also used. Snowball
sampling and chain-referral sampling has been viewed as an effective sampling technique
by researchers because it allows researchers to reach populations that may be hidden or
difficult to reach (Norris, Harrington, Grossman, Hemed, & Hindin, 2016; Waters, 2015).
When potential study participants contacted me, I sent an e-mail thanking them for their
interest and asked them to refer anyone that they think would benefit from my study (see
Addendum).
Sampling and Sampling Procedures
I used a convenience sample for this study and recruited participants from both a
private school in Chicago, IL., Walden University’s online participant pool,
Findparticipants.com, and Researchandme.com. As previously stated, snowball sampling
and chain-referral sampling were used as a contingency plan in order to secure the
minimum number of study participants. The Walden University online participant pool
consists of members of the Walden community, which includes Walden University

86
students, faculty, and employees and utilizes SurveyMonkey to gather information from
its participants. The private school in Chicago, IL consisted of 55 employees and 200
parents of the currently enrolled students. An associate degree is the minimum education
level of employees that are among the teaching staff of the private school in Chicago, IL.
The private school in Chicago, IL also allowed me the opportunity to recruit obese and
overweight women, which was the target of this study. Findparticipants.com and
Researchandme.com are research panel databases that consist of study participants
located worldwide that have voluntarily enrolled because they are interested in
participating in research studies. Findparticipants.com panel of participants reside in 129
countries, are 16 years of age and older, various ethnicities and educational levels
(Findparticipants.com, 2019). Researchandme.com consists of thousands of panel
participants that are located nationwide (Researchandme.com, 2019). I utilized
SurveyMonkey because it is an internet survey tool that can be customized by any
researcher.
The goal of the research was to compare the potential changes in food addiction
scores between groups. To achieve statistically significant results, the sample size for this
study was at least 68 completed participants to potentially detect a significant difference
in food addiction, as measured by the Yale Food Addiction Scale between groups. I used
G*Power software to calculate the sample size for this study. G*Power allows
researchers to conduct a statistical test to conduct a power analysis (Faul Erdfelder, Lang,
& Buchner, 2007). I utilized an ANCOVA to allow for control of the differences in pre-
test scores between the groups during this quasi-experiment (Hintz et al., 2015). Taking

87
this approach allowed me to make an unbiased comparison on the Yale Food Addiction
Scale post-test. When using G*Power, I inputted the following parameters: a power of
.80, a two-tailed alpha level of .05, and Cohen’s d of .5 for a medium effect size, and a
pretest-posttest correlation of .70. These parameters yielded the necessary sample size for
the research question, which was 34 for each group, with N = 68.
Procedures for Recruitment, Participation, and Data Collection
I recruited female study participants who are overweight and obese and who met
the additional study criteria from a private school in Chicago, IL., Walden University
online participant pool, Findparticipants.com, and Researchandme.com. The
Advertisement for Study was featured in the private school’s bi-weekly newsletter with
an invitation to contact me if interested in participating in the study (See Appendix E).
The Center for Research Quality sent out an email to alert Walden University online
participant pool users that my Advertisement for Study has been posted to the Center for
Research Quality virtual bulletin board. The Advertisement for Study also featured an
invitation to contact me if interested in participating in the study. Findparticipants.com
and Researchandme.com featured my Advertisement for Study in their regularly
scheduled e-mails that are sent out to members of their participant pool. For tracking
purposes, both Findparticpants.com and Researchandme.com removed my contact
information and directed potential study participants to click on a link that alerted me of
potential study participant’s interest. Both Findparticipants.com and Researchandme.com
compiles the information of all interested study participants on a dashboard section of
their websites for the researcher to view and track recruiting progress.

88
If someone contacted me via phone, I discussed the information featured on the
Advertisement for Study page and the Consent Form. If the potential participant was
interested in participating in the study, I confirmed that the potential study participant
meets the eligibility criteria and collected their contact information which included their
first and last name, and their e-mail address. I shared with the potential study participant
that in 24 hours they will receive an e-mailed invitation to click a SurveyMonkey link
that will contain a consent form and a survey. I also shared with the potential study
participant that once they complete the survey and it is confirmed that they meet the
study criteria that for four weeks I sent various health information for them to read. Also,
at the end of four weeks, I asked potential study participants to complete a knowledge
quiz based on the health information that they read and to re-take the survey they
completed in week one. Finally, I encouraged potential study participants to contact me if
they had any questions and confirmed that they had my contact information.
Potential study participants that contacted me via e-mail, were provided the
Advertisement for Study page with an invitation to participate in the study if the potential
study participant meets the eligibility criteria. I also included the SurveyMonkey link and
asked potential study participants to reply to my email to inform me if they are not
interested in participating in the study. Potential study participants were also encouraged
to contact me directly if they had additional questions. My contact information was
provided at the end of the e-mail. Potential study participants that contacted me but
hadn’t completed a SurveyMonkey survey nor indicated they are not interested in

89
participating in my study were contacted in 48 hours and extended an invitation to
participate in my study once a week for three months.
The SurveyMonkey link contained the consent form, demographic questionnaire,
and Yale Food Addiction Scale (Appendix E). Potential study participants had the
opportunity to review the consent form which described my study. The consent form
provided more details about the study and stated that this study will give participants two
types of health information and study the effect. Specifically, increasing awareness of
foods that have been linked to increasing food addiction (see Appendix F). Study
participants were also given the opportunity to indicate that they are giving informed
consent by selecting “Yes” or “No” on the “Informed Consent to Participate in a
Research Study” section of the online survey. Participants were asked to provide their e-
mail addresses so that they may receive pre-test, weekly health information, and a post-
test and knowledge quiz at the end of the study.
The next section of the online survey featured the demographic questionnaire. The
demographic questionnaire served as a screening questionnaire and was used to
determine which study participants meet study criteria and to collect data for this study.
The demographic questionnaire collected the following information: mental health
diagnosis, treatment for anxiety or depression, in the past six months, have you been
pregnant, are you currently pregnant, highest level of education completed, gender, age,
weight, height, and ethnicity. Height and weight information were used to describe study
participants and calculate BMI. BMI was one of the selection criteria for this study. I then
calculated the BMI and used this information to describe my study participants.

90
Participants that selected answers that did not meet study criteria were redirected to a
disqualification page. The disqualification page displayed the message “Thank you for
your interest in this study, I am sorry, but you do not meet one of the following study
criteria. Female, at least 18 years of age, not currently pregnant or pregnant in the last six
months, and overweight or obese. However, as a thank you for expressing interest in the
study, all participants that have expressed interest in the study will be emailed the health
information once the study concludes.” Participants were invited to contact me if they
have any questions. My contact information was displayed at the end of the message.
Participants were directed to the next part of the SurveyMonkey online survey
system which contained the survey instrument (Yale Food Addiction Scale) which was
used to collect data for this study. I converted the Yale Food Addiction Scale into an
electronic format and deployed it using the online survey system SurveyMonkey
(SurveyMonkey, 2015). No modifications were made to the scale. Burrows et al. (2017)
administered the Yale Food Addiction Scale online to investigate food addiction in
children.
I ensured that participants were presented with information stating that they can
leave the study at any time, and that they were provided with information detailing exit
procedures for the study. I featured this information beneath the first instructions
contained in the online survey, followed by the Yale Food Addiction Scale. Once
participants answered the Yale Food Addiction Scale questions, the last page (closing
page of the survey) displayed the message - “Thank you for completing our survey! This
study is confidential, and the researcher will hold all responses in the strictest

91
confidentiality. You are invited to contact the researcher if you have any questions.” on
the study participant’s computer screen. My contact information was provided at the end
of the above message.
The study took place over the course of four weeks. The health information
distributed was different for the social cognitive theory -based health information group
than the non- social cognitive theory-based health information group. Once a week, both
groups received health information presentations distributed via e-mail designed to
increase health awareness of food addiction and overeating. Furthermore, study
participants received a weekly pre-recorded webinar that reviewed the information
covered in the health information presentations. Study participants viewed these pre-
recorded webinars once they clicked a link in their e-mail. The eLearning software Adobe
Presenter 11.1 was used to play the pre-recorded webinars (Adobe Presenter 11.1). This
software was selected because it gave me the ability to confirm that the webinar has been
viewed. These weekly pre-recorded webinars increased the likelihood of reviewing the
information. To confirm the viewing of the pre-recorded webinar, I examined the
“counter” on the webinar software weekly. If the counter indicated that a low number of
people are listening to the webinar, I contacted study participants within three days via e-
mail to remind each participant that this information is available in pre-recorded webinar
format.
The weekly schedule over the course of four weeks included the following: The
beginning of the week entailed e-mailing the health information. Towards the end of the
week: distributing the weekly pre-recorded webinar. The beginning of the first week and

92
towards the end of the fourth week: Participants completed the Yale Food Addiction
Scale (see Appendix A) via the SurveyMonkey link that to be provided via e-mail. The
health information specifically discussed components of social cognitive theory, such as
discovering and maximizing one’s self-efficacy for food addiction symptoms. This health
information also expounded upon how to fulfill outcome expectations in order to
overcome food addiction symptoms and learn about facilitation tools, and how to apply
these tools to symptoms of food addiction. Finally, this health information discussed how
to self-regulate oneself in the face of food addiction. The social cognitive theory -based
health information group’s presentations addressed the following over the course of four
weeks:
• Week 1: Is Your Food Helping You or Hurting You? Principles of Food
addiction and Perceptions of Food (Increasing awareness about food addiction
and self-efficacy). Finding Your “Happy Place” (Setting up a Food Plan).
Changing Expectations about Healthier Foods (Addressing outcome
expectations)
• Week 2: Just Say Yes!!!! (Self-regulation, increasing self-efficacy, and
facilitation by providing tools and suggesting alternatives to commonly
consumed foods that contain HFCS and MSG to reduce and eliminate food
addiction).
• Week 3: Sexy and Energetic You – And You Can Eat Dessert!!! – Sexy
desserts and sweets (Facilitation – providing tools, self-instruction, and
outcome expectations);

93
• Week 4: Seven Tricks to Sticking to Your Goals – (Self – regulation and
facilitation)
During the third week of the study, I sent study participants a “thank you” e-mail.
This email thanked the participants for their participation, and alerted them that they are
approaching the end of the study. The e-mail asked participants to refer anyone that they
knew that they think would like to participate in this study. I also asked participants to
reply to the e-mail if they were interested in receiving the results of the study, and will
provide participants who were part of the non- social cognitive theory health information
group the social cognitive theory -based health information one week after the study
ends. During the fourth week of the study, a SurveyMonkey link was e-mailed to both
groups of participants that directed participants to take a brief knowledge quiz. The
knowledge quiz was based on the contents of the health information study participants
have received over the course of four weeks. This was to confirm that study participants
have reviewed the health information. The knowledge quizzes also provided an
opportunity for study participants to apply the newly learned information. There were
two knowledge quizzes containing 12 questions. One knowledge quiz – the social
cognitive theory knowledge quiz – was based on the social cognitive theory-based health
information participants had been receiving over the course of four weeks (see Appendix
H). The second knowledge quiz – the non- social cognitive theory knowledge quiz – was
based on the non- social cognitive theory-based health information participants had been
receiving over the course of four weeks (see Appendix I). Once a participant completed
the quiz, a score indicating the percentage of questions answered correctly was displayed.

94
Table 1 depicts the study’s four-week schedule for both the non- social cognitive theory
and social cognitive theory group.
Table 1
Study Schedule
Monday
Tuesday
Wednesday
Thursday
Friday
Saturday
Week 1
Yale Food
Addiction
Scale
Health
information
Weekly
Pre-Recorded
Webinar
Demographic
Survey
Week 2
Health
information
Weekly Pre-
Recorded
Webinar
Week 3
Health
information
Weekly Pre-
Recorded
Webinar
&
Thank You -
Email
Week 4
Health
information
Weekly Pre-
Recorded
Webinar
&
Knowledge
Quiz
Yale Food
Addiction
Scale
The non- social cognitive theory health information study participants received
weekly health information as well, but it differed from what the social cognitive theory
health information study participants received. The non- social cognitive theory health
information was educational only–none of the social cognitive theory components were
provided–only general information about healthy food. The titles of the study
participant’s health information were as follows:

95
• Week 1: Is Your Food Helping You or Hurting You? (Increasing awareness
about food addiction)
• Week 2: Just Say Yes!!!! (Providing tools and suggesting alternatives to
commonly consumed foods that contain HFCS and MSG to reduce and
eliminate food addiction)
• Week 3: Sexy and Energetic You – And You Can Eat Dessert!!! (Facilitation
– providing tools, self-instruction, and outcome expectations)
• Week 4: Seven Tricks to Sticking to Your Goals (Seven recommendations to
help study participants adhere to goals. Providing tips and tricks provide study
participants the opportunity to increase their ability to develop self-regulatory
functions in order to sustain newly established behavior [Bandura, 1969]).
Instrumentation and Operationalization of Constructs
I administered all components of this study, including the Yale Food Addiction
Scale. This scale measured food addiction, the dependent variable. The Yale Food
Addiction Scale was appropriate to this study because this scale measures potential
changes in food addiction between two groups of overweight and obese women
(Gearhardt et al., 2009). The first group received social cognitive theory-based health
information, and I compared it to the second group, which did not receive social
cognitive theory-based health information.
Yale Food Addiction Scale
The Yale Food Addiction Scale, which measured the dependent variable in this
proposed study, was published in 2009 and was developed by Gearhardt, Corbin, and

96
Brownell (Gearhardt et al., 2009). I did not need permission for the use of the scale in this
study because it is publicly available. The Yale Food Addiction Scale was utilized in this
study because it is the only instrument of its kind that measures levels of food addiction.
Taking this approach was important because food addiction shares similar neurological
pathology with addiction among people who are overweight and obese. The scale also
identifies patterns in eating behavior that are common to those that share addictions in
other areas, such as binge eating and alcoholism (Gearhardt et al., 2009). It measures
eating behavior and has been used with the following populations: those experiencing
behavioral addiction such as eating disorders, emotional eating behaviors, people who are
overweight (Gearhardt et al., 2009), and self-identified food addicts (Ruddock, Dickson,
Field, & Hardman, 2015). It consists of 27 questions (e.g., “I have found that I have
elevated desire for or urges to consume certain foods when I cut down or stop eating
them”). Fifteen questions are scored using a Likert scale scoring system from 0 to 4, with
0 (never), (once a month), 2 (2-4 times a month), 3 (2-3 times a week), and 4 (4 or more
times a day). Eight questions are scored using a dichotomous scoring system of “Yes” or
“No”.
To calculate scores, I used a combination of dichotomous scoring and frequency
scoring. For questions that are potentially probing in nature (i.e. – continuing to consume
foods even though the study participant has experienced emotional or physical problems),
I used dichotomous scoring (Gearhardt et al., 2009). Eight questions were scored
dichotomously. For these questions, participants selected 0 if they have never
experienced a food addiction symptom and selected 1 if they have experienced a

97
symptom. For behaviors that could potentially occur occasionally for non-problem eaters
(i.e. emotional eating, dieting) frequency scoring was used. Gearhardt et al. (2009) used
the following approach to score the Yale Food Addiction scale: “For the dichotomous
items, two different scores were created based on diagnostic criteria: a dichotomous
diagnosis (yes/no) and a symptom count (0-7)” (p. 434). I will consider the diagnostic
version met, which resembles a diagnosis of substance dependence, criteria if participants
endorse three or more criteria as well as at least one of the two clinical significance items
(Gearhardt et al., 2009). The endorsement of at least one of the two clinical significance
items implies that the participant has experienced impairment or distress (Gearhardt et al.,
2009). Participants that indicated they have experienced impairment or distress were
referred to support services that are affordable, free, and based on a sliding fee scale at
the end of the study. The consent form also featured support services information that is
affordable, free, and based on a sliding fee scale. All participants will receive a one-page
summary of completed research results following participation. The symptom count score
is the sum of the seven diagnostic criteria. “The median number of criteria met for this
sample was 1, and 11.4% of participants in the sample met criteria for food addiction
(Gearhardt et al., 2009)” (p. 434).
First, I calculated food addiction symptoms with a continuous “symptom count”
(Burmeister et al., 2013; Gearhardt et al., 2009). Second, another section of the scale
featured a “diagnostic” scoring symptom option. Completion of this section provided
information about whether a person meets food addiction criteria. An individual met the
criteria of food addiction if they indicated that they exhibited three or more symptoms,

98
and also experienced significant impairment or distress (Burmeister et al., 2013;
Gearhardt et al., 2009).
This scale has been tested on clinical patients (64% women, and 18% of
participants were overweight) and assessed and found to be reliable and valid based on
several factors (Gearhardt et al., 2009). The content validity of the scale is founded in
questions that are based on substance dependence and behavioral addictions criteria in the
DSM-IV-TR (American Psychiatric Association [DSM-IV-TR], 2000). The Yale Food
Addiction Scale is comprised of the following scales: The Binge Eating Scale, BIS/BAS
Reactivity Scale, Eating Troubles Module, Emotional Eating Scale, Rutgers Alcohol
Problem Index, and the Daily Drinking Questionnaire. Gearhardt et al. (2009), examined
correlations between the Yale Food Addiction Scale and other established eating
pathology predictors to assess convergent validity. The correlations were found to be
statistically significant ranging from .46 to .61 (Gearhardt et al., 2009). Gearhardt et al
(2009) selected these scales because they are frequently used to assess consumption of
high fat and high sugar foods. Gearhardt et al (2009) adapted questions from these scales
to properly assess food addiction levels.
Once questions were selected, developed, and revised from these scales and
indexes, Gearhardt et al. (2009) and a pool of experts specializing in the fields of
addiction, obesity, and eating pathology reviewed item content and wording. This review
was to ensure that the questions adequately assessed what they were supposed to
measure. Gearhardt et al. (2009) also examined scoring options such as dichotomous,

99
frequency and Likert scale options. To effectively capture diagnostic criteria, Gearhardt
et al. (2009) chose dichotomous and frequency scoring.
The scales and indexes used to form the foundation of the Yale Food Addiction
Scale have been proven to be reliable (Gearhardt et al., 2009). For example, the internal
reliability of the Binge Eating Scale is Cronbach’s α = .93 (Gearhardt et al., 2009). The
internal reliability of the BIS/BAS Reactivity scales are .78 and .71 respectively. The
Eating Troubles Module internal reliability scale is .91. The Emotional Eating Scale has
an internal reliability of .95. The Rutgers Alcohol Problem Index had an internal
reliability of .95. The Daily Drinking Questionnaire had an internal reliability of .83
(Gearhardt et al., 2009).
Gearhardt et al. (2009) explored and established reliability by utilizing the Mplus
statistical package. The researchers used this statistical package to explore the number of
underlying factors of the questions of the Yale Food Addiction Scale (excluding
questions that pertain to clinical significance). In addition, the researchers used the Mplus
statistical package to conduct an exploratory factor analysis for the dichotomous data.
One item earned a low factor loading of .33 and the researchers removed it because it did
not strongly correlate. Gearhardt et al. (2009), plotted four factors based on eigenvalues
greater than one, but plotting of each factor suggested a single factor structure. Good
internal reliability (Kuder-Richardson α = .86) resulted from all factor loadings for the
single factor of .50 or higher. Gearhardt et al. (2009) also conducted a parallel factor
analysis on seven dichotomous diagnostic criteria and succeeded in identifying a single

100
factor structure. Factor loadings for the single factor were .69 or higher (Gearhardt et al.,
2009). The single factor yielded adequate internal reliability (Kuder-Richardson α = .75).
Gearhardt et al. (2009) established validity three ways: convergent, discriminant,
and incremental. They first sought to examine convergent validity by examining the
correlations between scores on the Yale Food Addiction Scale and other scales that
gauged and assessed eating behavior, such as emotional eating (Gearhardt et al., 2009).
What they found was that the Yale Food Addiction Scale was statistically significant with
scores ranging from .46 to .61 (Gearhardt et al., 2009).
When Gearhardt et al. (2009) explored discriminant validity, they compared
correlations between Yale Food Addiction Scale scores and scores on measures of related
but independent constructs such as alcohol use, related problems, and impulsivity.
However, they found no significant correlations between the Yale Food Addiction Scale
scores and alcohol consumption. However, they did find statistically significant
correlations of .16 and .17 between Yale Food Addiction Scale scores and alcohol
problems (Gearhardt et al., 2009). The BIS (behavioral inhibition scores) and Yale Food
Addiction count scores and the Yale Food Addiction Scale diagnostic scores experienced
small but significant correlation. Furthermore, Behavioral Activation scores were not
significantly correlated with Yale Food Addiction Scores.
Gearhardt et al. (2009) used hierarchical multiple regression to measure
incremental validity of the Yale Food Addiction Scale. To predict binge eating pathology,
they entered the Yale Food Addiction Scale scores in addition to other measures of eating
pathologies, such as emotional eating and eating troubles. The problem eating attitudes, t

101
= 6.98, β = .37, p < .01, and emotional eating, t = 9.77, β = .53, p < .001 both registered
as significant predictors of the continuous binge eating measure, which accounted for
49.9% variance. After Gearhardt et al. controlled for variance accounted for at step one of
the model, the symptom count version of the Yale Food Addiction Scale was a significant
predictor in step two of the model. This symptom count version of the Yale Food
Addiction Scale, in turn, accounted for an additional 14.8% of unique variance in binge
eating scores (Gearhardt et al., 2009).
Finally, the diagnostic version of the scale yielded similar results. Emotional
pathology and emotional eating scores were significant predictors of binge eating; they
were so statistically significant that it accounted for 47.4% of the variance of the
regression model (Gearhardt et al., 2009). Once the researchers controlled variance in
step one of the regression model, the diagnostic version of the Yale Food Addiction Scale
accounted for 5.8% of the unique variance. This study has been used with a population
that was primarily Caucasian and female. The study participants were on average 20.11
years old, 72.5% Caucasian, 18.5% Asian-American, and 9% African-American
(Gearhardt et al., 2009). The study primary consisted of women (64.2%), although men
participated in the study as well (35%) (Gearhardt et al., 2009).
Operational Definitions of Variables
Food addiction. Certain foods, whether seen or eaten, activate the same brain
circuitry that is activated by addictive drugs, and thus regulates dietary behavior (Rogers,
2011). Confirmation of food addiction and levels of food addiction can be measured with
the Yale Food Addiction Scale.

102
Social cognitive theory-based health information. Health information that will
share material about healthier food choices and how consuming foods with food additives
MSG and HFCS adversely impact the body and encourages overeating (Insawang et al.,
2012; Lowndes et al., 2012). The health information will also include instructions on how
to avoid foods that contain MSG and HFCS. This information will also list food
alternatives to popular foods that contain MSG and HFCS.
Data Analysis Plan
Preliminary Analyses
I collected all data and information from SurveyMonkey and downloaded it into
SPSS version 25.0. I minimized the possibility of missing data and information by
programming the survey delivery instrument (SurveyMonkey) to prevent survey
participants from skipping questions. However, before analyzing the data, I performed
data cleaning to ensure the accuracy of the data before analyzing. Data cleaning entailed
verifying that all entered information has values within the expected range of the
corresponding question. Additionally, I sorted the data and reviewed it to ensure that
study participants did not provide irrelevant/inappropriate answers to any survey
questions. However, no study participant provided irrelevant/inappropriate answers. In
addition, I performed an analysis of demographical variables, which consisted of mean,
mode, median, frequency distribution, mean and standard deviation of continuous study
variables and frequencies of categorical ones.
The software used to analyze the data was SPSS Statistics 25.0. Comparisons
were made between study participants in the social cognitive theory -based health

103
information group and participants in the non- social cognitive theory-based health
information group. The social cognitive theory -based health information group consisted
of health information featuring components of social cognitive theory, such as self-
efficacy and modeling; the non- social cognitive theory -based health information group
received standardized health information without social cognitive theory components. To
analyze the collected data, I first included descriptive statistics such as the mean, median,
mode, standard deviation, frequency, and percentage for the dependent variable and
relevant demographic variables (see Table 2, Table 3, Table 4, Table 5, and Table 6).
Table 2
Descriptive Statistics
Total Symptom Count
Scores
Total Food Addiction
Scores
Pre-Test
Post-Test
Pre-Test
Post-Test
Mean
4.12
3.27
4.58
3.62
Median
4.00
3.00
5.00
3.00
Mode
5
2
5
2
Standard Deviation
1.609
1.752
1.915
2.094
Table 3
Descriptive Statistics
Non-SCT Based Health
Information Group
Symptom Count Scores
SCT Based Health
Information Group
Symptom Count Scores
Pre-Test
Post-Test
Pre-Test
Post-Test
Mean
3.90
2.98
4.33
3.57
Median
4.00
3.00
5.00
3.50
Mode
4
2
5
2
Standard Deviation
1.411
1.569
1.776
1.889

104
Table 4
Descriptive Statistics
Non-SCT Based Health
Information Group
Food Addiction Scores
SCT Based Health
Information Group
Food Addiction Scores
Descriptive statistics
Pre-Test
Post-Test
Pre-Test
Post-Test
Mean
4.21
3.21
4.95
4.02
Median
4.00
3.00
5.00
4.00
Mode
4
3
5
2
Standard Deviation
1.539
1.868
2.186
2.247
Table 5
Descriptive Statistics
Non-SCT Based Health
Information Group
Symptom Count Frequencies
SCT Based Health Information
Group
Symptom Count Frequencies
Frequency
Pre-Test
Post-Test
Pre-Test
Post-Test
0
n/a
2.4% (n = 1)
2.4% (n=1)
2.4% (n = 1)
1
4.8% (n = 2)
14.3% (n = 6)
7.1% (n = 3)
11.9% (n = 5)
2
9.5% (n = 4)
26.2% (n = 11)
9.5% (n = 3)
21.4% (n = 9)
3
23.8 (n = 10)
23.8 (n = 10)
9.5% (n = 4)
14.3% (n = 6)
4
31% (n = 13)
16.7% (n = 7)
11.9% (n = 5)
14.3% (n = 6)
5
19% (n = 8)
9.5% (n = 4)
31% (n = 13)
19.0% (n = 8)
6
7.1% (n = 3)
4.8% (n = 2)
23.8% (n = 10)
9.5% (n = 4)
7
4.8% (n = 2)
2.4% (n = 1)
4.8% (n = 2)
7.1% (n = 3)

105
Table 6
Descriptive Statistics
Non-SCT Based Health
Information Group
Food Addiction Frequencies
SCT Based Health Information
Group
Food Addiction Frequencies
Frequency
Pre-Test
Post-Test
Pre-Test
Post-Test
0
n/a
2.4% (n = 1)
2.4% (n=1)
2.4% (n = 1)
1
4.8% (n = 2)
14.3% (n = 6)
7.1% (n = 3)
9.5% (n = 4)
2
4.8% (n = 2)
21.4% (n = 9)
7.1% (n = 3)
23.8% (n = 10)
3
23.8% (n = 10)
26.2 (n = 11)
11.9% (n = 5)
9.5% (n = 4)
4
26.2% (n = 11)
16.7% (n = 7)
2.4% (n = 1)
9.5% (n = 4)
5
21.4% (n = 9)
4.8% (n = 2)
21.4% (n = 9)
16.7% (n = 7)
6
11.9% (n = 5)
9.5% (n = 4)
21.4% (n = 9)
11.9% (n = 5)
7
4.8% (n = 2)
2.4% (n = 1)
19% (n = 8)
9.5% (n = 4)
8
2.4% (n = 1)
n/a
4.8% (n=2)
7.1% (n = 3)
9
n/a
2.4% (n = 1)
2.4% (n = 1)
n/a
Main Analyses
Research Question 1. The dependent variables were food addiction symptoms
and food addiction scores. To examine potential changes in food addiction, I analyzed
scores on the Yale Food Addiction Scale (see Appendix A) using an ANCOVA to
examine changes between the pre-test and post-test with the pre-test as a covariate. The
associated F-test with the pre-test as the covariate determined if there is a significant
difference between the two comparison groups and, at least in part, the effectiveness of
the social cognitive theory-based health information. I utilized a .05 alpha level for
testing the null hypothesis.
The first research question as presented in chapter one, is: What is the extent of
the difference in food addiction post-test scores as measured by the Yale Food Addiction
Scale, among overweight and obese women who receive Social Cognitive Theory-based

106
health information compared to overweight and obese women who receive non-Social
Cognitive based health information?
The hypotheses are as follows:
H01. When comparing the impact of social cognitive theory -based health
information with non-social cognitive theory-based health information presented to
overweight or obese women, there is no significant difference in food addiction posttest
scores (while controlling for differences in pretest scores) as measured by the Yale Food
Addiction Scale.
HA1. When comparing the impact of social cognitive theory-based health
information with non- social cognitive theory-based health information presented to
overweight or obese women, there is a significant difference in food addiction posttest
scores (while controlling for differences in pretest scores) as measured by the Yale Food
Addiction Scale.
To examine the effect of the independent variable of social cognitive theory-based
health information on the dependent variable of food addiction, I analyzed scores on the
Yale Food Addiction Scale (Appendix A) using an ANCOVA analysis. In addition, I
tested for univariate outliers, normality, linearity, and homogeneity of variance,
homogeneity of regression slopes, and reliable measurement of the covariate. This
approach was recommended by Pallant (2016).
Research Question 2. Although the primary focus of this study is to analyze
differences in food addiction scores among overweight and obese women who receive
social cognitive theory-based health information compared to overweight and obese

107
women who receive non- social cognitive theory-based health information, it is possible
that food addiction symptoms could change as well. Therefore, I created a second
research question. This research question examined differences between the two groups
of overweight and obese women who received social cognitive theory-based health
information and non- social cognitive theory-based information.
The second research question as presented in chapter one, is: What effect does
Social Cognitive Theory-based health information have on symptom count post-test
scores, as measured by the Yale Food Addiction Scale, among obese and overweight
women compared to obese and overweight women who receive the non-Social Cognitive
based health information?
The hypotheses are as follows:
H02. When comparing the impact of social cognitive theory -based health
information with non- social cognitive theory -based health information presented to
overweight or obese women, there is no significant difference in symptom count posttest
scores as measured by the Yale Food Addiction Scale.
HA2. When comparing the impact of social cognitive theory-based health
information with non-social cognitive theory-based health information presented to
overweight or obese women, there is a significant difference in symptom count posttest
scores as measured by the Yale Food Addiction Scale.
To examine the effect of the independent variable of social cognitive theory-based
health information on the dependent variable of food addiction symptom count, I
analyzed scores on the Yale Food Addiction Scale (Appendix A) using an ANOVA and

108
post hoc t-test to examine changes between the pre-test and post-test. Taking this
approach allowed me to understand the differences between the means of the independent
variable.
Threats to Validity
The study is quasi-experimental in nature; therefore, I considered potential threats
to external and internal validity. I minimized potential threats to external validity six
ways. First, selection of study participants, second, experimental setting, third, history,
fourth, changes to food addiction scores, fifth, utilizing a convenience sample, and sixth,
interaction of testing and post-test (Creswell, 2009).
External Validity
I attempted to minimize potential threats to external validity by managing the
selection of study participants two ways. First, I stated the desired characteristics of the
participants in the study and when recruiting potential study participants (Creswell,
2009). I strived to avoid overgeneralizing study results by limiting results to the sample,
but provided new information that may serve to inform future studies and, potentially,
inform future clinical practices when dealing with similar populations.
Second, I also minimized the threat to external validity by minimizing changes to
the experimental setting. Due to the nature of the study being quasi-experimental in
nature with human test subjects, I had no control of the study participant’s environment,
and therefore communicated to the study participants that they should strive to maintain
their normal routine. Third, I minimized the potential external threat of history by

109
articulating the duration of the study. In addition, I discussed what transpired during each
week of the study.
Fourth, I made changes to food addiction scores that may not be an accurate
representation of the cause-and-effect relationship to the health information provided.
Although a true experiment would have been preferred, it would have been difficult to
create a closed environment in which study participants had access to only particular
types of foods. In addition, the results would have been difficult to replicate, which
would create an inability to generalize the results. Essentially, placing study participants
into a controlled setting and selecting their daily meals for four weeks is not realistic or
feasible.
The fifth threat was utilizing a convenience sample instead of a true random
sample from a target population. Although a true sample from a target population would
have been preferred, it would have been difficult to procure due to time constraints.
Perhaps future studies will be able to pursue this line of sampling. Finally, another
external threat was the possibility of the interaction of testing and post-test. This could
have occurred due to the pre-test potentially decreasing study participant sensitivity
(Campbell & Stanley, 1963). I hoped to address this issue by allowing some time to pass
between the pre-test and post-test. It is, for this reason, that I scheduled study participants
to take the post-test during the fourth week of the study.
Internal Validity
Although researchers are still uncovering new evidence about food addiction,
overall, there is still much to learn about food addiction theory, and how symptoms of

110
food addiction can be addressed. Despite efforts to minimize or eliminate threats to
internal validity, two threats bear mentioning. The first threat to internal validity was
mortality. Mortality occurs when participants drop out of a study before the study ends
(Creswell, 2009). To reduce the chances of mortality, I scheduled the duration of this
study to end in four weeks. Most health behavior studies usually last at least 12 weeks,
and therefore experience some degree of mortality. However, it is possible to observe
improvement in less than four weeks. Schneider et al. (2016) found that healthy lifestyle
changes, which entailed increasing consumption of fruit and vegetables, could take place
in three weeks. It was my hope that the duration of this study was long enough to be
adequate, yet short enough to prevent loss of interest and participation. To offset the
threat of mortality, Creswell (2009) also recommended that researchers enlarge their
sample. Therefore, I worked to recruit more than the minimum required amount of total
study participants.
The final threat to the internal validity was sample selection. According to
Creswell (2009), selection bias occurs when the researcher selects study participants who
have certain characteristics that predispose them to have certain outcomes. This study
may be biased because the study participants were all be female, and overweight or
obese. For example, Gearhardt et al.’s (2009) landmark food addiction study consisted of
18.7% overweight participants and 73.5% normal weight participants. Gearhardt et al.
(2009) found evidence of food addiction. Finally, this study may be biased because of the
use of female study participants, as the results cannot be applied to men.

111
Ethical Procedures
To maintain ethical integrity, I submitted the IRB application to Walden
University to gain access to participants and to ensure that the rights and welfare of
participants are protected. In addition, the IRB application described how my study
complied with ethical research policies and protocols. This study was created with ethical
considerations always being at the forefront of each step of the process, from the design
of the study to analysis to distribution of results. I obtained approval from Walden
University’s IRB before collecting data. Upon securing IRB approval, I included a
confirmation number in the final dissertation (Approval number 05-03-18-0326424).
I addressed ethical concerns related to recruitment materials and processes by
making sure that participants are aware of the study’s procedure, the risks and benefits of
the study, and the fact that participation in this study was voluntary. I communicated this
in the initial message of the SurveyMonkey survey. In addition, study participants were
alerted to their rights, that the study is confidential, and that I will hold all responses in
the strictest confidentiality on the final survey page of the SurveyMonkey survey and the
consent form (see Appendix G). Additionally, weekly correspondence provided my
contact information should study participants want to communicate with me to ask
additional questions.
The plan to protect confidential data entailed first recording all data and
information in an excel spreadsheet. I then stored this information in three places: first on
my computer; second, I uploaded the data to my external storage drive; and third, I
uploaded the data to Dropbox, the cloud-based storage system. I was the only one with

112
access to the data and used the data solely for the purpose of research. I plan to destroy
data after seven years, as per the recommendation of the American Psychology
Association (Bersoff, 2008). There are no other ethical issues or conflicts of interest.
Summary
Chapter 3 began with the study’s introduction and discussed the purpose of the
study and examined the research design and rationale. This includes but is not limited to
the approach, the study variables, and the design choice. Next, I discussed the study’s
methodology, sampling and sampling procedures. This includes but is not limited to
sample selection, characteristics of the study’s participants, and rationale for approaches
taken to achieve statistically significant results. Finally, I discussed procedures for the
recruitment, participation, and data collection, instrumentation and operationalization of
constructs, data analysis methods, validity, reliability, and finally ethical considerations.
In chapter 4, I will describe the data and information gathered for the study, and
repot study findings. Finally, in chapter 5, I will analyze the results of the study after
conducting a statistical analysis.

113
Chapter 4: Results
This study addressed the impact of health information based on social cognitive
theory on food addiction among obese and overweight women. Specifically, I looked at
how health information based on social cognitive theory may reduce consumption of food
additives including carbohydrates, high fructose corn syrup (HFCS), and monosodium
glutamate MSG. The research questions and hypotheses were the following:
RQ1. What is the extent of the difference in food addiction post-test scores as
measured by the Yale Food Addiction Scale, among overweight and obese women who
receive Social Cognitive Theory-based health information compared to overweight and
obese women who receive non-Social Cognitive based health information?
H01. When comparing the impact of social cognitive theory-based health
information with non-social cognitive theory -based health information presented to
overweight or obese women, there is no significant difference in food addiction posttest
scores (while controlling for differences in pretest scores) as measured by the Yale Food
Addiction Scale.
HA1. When comparing the impact of social cognitive theory-based health
information with non- social cognitive theory-based health information presented to
overweight or obese women, there is a significant difference in food addiction posttest
scores (while controlling for differences in pretest scores) as measured by the Yale Food
Addiction Scale.
RQ2. What effect does Social Cognitive Theory-based health information have
on symptom count post-test scores, as measured by the Yale Food Addiction Scale,

114
among obese and overweight women compared to obese and overweight women who
receive the non-Social Cognitive based health information?
H02. When comparing the impact of social cognitive theory-based health
information with non- social cognitive theory-based health information presented to
overweight or obese women, there is no significant difference in symptom count posttest
scores as measured by the Yale Food Addiction Scale.
HA2. When comparing the impact of social cognitive theory-based health
information with non- social cognitive theory-based health information presented to
overweight or obese women, there is a significant difference in symptom count posttest
scores as measured by the Yale Food Addiction Scale.
Chapter 4 includes a description of the data and the study findings. I present the
data collection time frames, quiz results, descriptive and demographic characteristics of
the sample, results of the ANCOVA and ANOVA analyses, and results of additional
statistical tests that emerged from the analysis of the primary hypothesis. I also include
tables and figures to demonstrate my study results.
Data Collection
The time frame for data collection was June 1, 2018 to November 27, 2018. The
recruitment required collecting data from a minimum of 68 obese and overweight women
from a private school in Chicago, IL and Walden University’s online participants pool.
After receiving approval from Walden IRB and recruiting from these two sources, I
collected data from two additional sources from September 18, 2018 to November 27,

115
2018. Although a minimum of 68 obese and overweight women (thirty-four for each
group) were required for this study, 173 women enrolled in the study and completed the
pretest. Once the study concluded, 84 women had completed the posttest.
The response rates were calculated from each research recruitment site based on
the number of study participants who clicked on the recruiting ad. Participants who
clicked on the recruitment ad were directed to the demographic survey administered
through SurveyMonkey. Participants could choose to complete the demographic survey
or decline to begin the survey by closing their browser window. For participants who
chose to complete the survey, SurveyMonkey e-mailed me a notification. I accessed the
survey responses and confirmed eligibility for the study by calculating the study
participants’ BMI. Eligible participants were notified that they were eligible for the study
and received the health information for the first week.
Three websites provided analytics such as the number of e-mails, electronic
newsletters, and electronic announcements containing the recruiting advertisement sent to
their respective participant pools. The websites Findparticipants.com and
Researchandme.com provided detailed analytic information. Walden University’s
participant pool provided the number of participants who expressed interest in the study,
which was calculated by clicking the featured study link. The private school in Chicago,
IL. featured the recruiting ad in their school newsletter that was sent to 200 people
consisting of parents and staff.
Websites such as Findparticipants.com, Researchandme.com, and Walden
University’s participant pool were required to respect the confidentiality of their

116
participants. Although most sites provided analytic information, they were unable to
display the e-mail address of their participants to me. Therefore, there was no way for me
to identify where most of the participants were recruited from. There was one exception:
Researchandme.com. Study participants who volunteered for studies in the
Researchandme.com website supplied their e-mail addresses and phone numbers as a
condition for participating. They were informed that I would contact them if selected for
the study. Researchandme.com provided me with the potential participants’ e-mail
addresses after I selected the participants desired for the study. One thousand seven
hundred and thirteen people in the Reseachandme.com participant pool viewed the
recruiting ad, and 12% (n = 205) clicked the link and contacted me expressing an interest
in participating in the study. After reviewing potential study participants’ responses, 101
participants were sent the SurveyMonkey link to begin the study. These participants were
selected from Researchandme.com for two reasons. The first was that study participants
met the selection criteria. The second reason was that more participants were needed for
the study. Overall, it appeared that 50% of the study participants had completed the
posttest. Therefore, although 200 Researchandme.com study participants expressed an
interest in the study, 20 additional participants were needed. Researchandme.com allows
researchers to purchase a certain amount of study participants for a set fee. For example,
a researcher can purchase access to segments of 50 participants, 100 participants, or 250
participants. Because I needed access to 100 participants to complete the study, 100
participants were selected. This accounted for an estimated 50% response rate of
participants who actually enrolled in the study, and 50% of study participants choosing to

117
not complete the posttest. This way if participants did not complete the posttest, there
would be enough participants to complete the study.
Overall, 173 people completed the pretest. One hundred sixty-one of them were
eligible for the study and met the BMI requirements. Two participants opted out of the
study before the study ended. Eight participants who indicated that they were overweight
did not meet the BMI criteria and had normal BMIs. Therefore, they were not included in
the study. A summary is provided in Table 7).
Table 7
Pre to Post Test Completion
Completed
Pre-Test
Met Study
Criteria
Did Not
Meet
Study
Criteria
Completed
Four Week
Study
Completed
Post Test
Percent Post Test
Completion
173
161
10
161
84
52%
Note: 52% post-test completion calculated 24/161 = .52. Converted decimal to percent
– 0.5217 * 100 = 52.17
Knowledge Quizzes
As noted in chapter three, study participants from both groups that completed the
four-week study were sent two brief 12 question knowledge quizzes via a SurveyMonkey
link. The knowledge quiz for the social cognitive theory-based health information group
was based on the social cognitive theory-based health information that study participants
had received for four weeks (see Appendix H). The knowledge quiz for the non- social
cognitive theory-based health information group was based on the non- social cognitive
theory-based health information that study participants had also received for four weeks
(see Appendix I). Upon completing the quiz, a score displayed the percentage of

118
questions answered correctly at the top of the study participants’ computer screen. The
knowledge quizzes served two purposes: First, to confirm that study participants
reviewed the health information. Second, to provide an interactive way for study
participants to apply their newly learned health information.
Once a week for four weeks, study participants that completed the study received
a reminder which included the SurveyMonkey link to complete the knowledge quiz. The
reminder stated the following: “Also, once you finish reviewing your information, please
take this fun quiz to see how much you remember!! The quiz takes less than five minutes
to complete.” No study participants completed the knowledge quizzes. Due to the lack of
response from study participants, the reminder message was revised and sent during the
fifth week and stated the following: “Check What You Have Learned. Ever wonder if
you REALLY remember how to change your eating habits? Here’s your chance to check
out what you have learned to see how much you remember!! This is not graded and you
cannot pass or fail.” This reminder was sent to study participants that completed the study
once a week for four additional weeks. However, no study participants completed the
knowledge quizzes.
By the ninth week, due to continued lack of knowledge quiz completion, the same
reminder message, “Check What You Have Learned. Ever wonder if you REALLY
remember how to change your eating habits? Here’s your chance to check out what you
have learned to see how much you remember!! This is not graded and you cannot pass or
fail” was sent three times a week (every other day) until the end of the study. Study
participants began to complete the knowledge quiz. Ten study participants from the social

119
cognitive theory health information group and eight study participants from the non-
social cognitive theory health information group completed the knowledge quizzes. The
overall score for study participants from the social cognitive theory health information
group was 88% and the overall score for the non- social cognitive theory health
information group was 98%. The minimum score for the social cognitive theory-based
health information group (n = 10) was 69%, and the highest score was 100%. The
minimum score for the non- social cognitive theory-based health information group (n =
8) was 79% and the highest score was 100%.
Prerecorded Webinars
Weekly, study participants received pre-recorded narrated webinars. These
webinars reviewed the week’s health information. The pre-recorded webinars were sent
to increase the likelihood and convenience of reviewing the health information. I
confirmed that the pre-recorded webinars were viewed by examining the webinar
software “counter” in Adobe Presenter 11.1 (Adobe Presenter 11.1). The number of study
participants that viewed the webinars started slowly for the first week, however, the
number of study participants that viewed the webinars began to increase. The first week,
study participants from the social cognitive theory-based health information group
viewed the webinars from the first week six times. The non- social cognitive theory-
based health information group viewed the webinars from the first week three times. The
second week, participants from the social cognitive theory-based health information
group viewed the webinars from the second week ten times. The non-social cognitive
theory-based health information group viewed the webinars from the second week 54

120
times. The third week, study participants from the social cognitive theory-based health
information group viewed the webinars from the third week 38 times. The non-social
cognitive theory-based health information group viewed the webinars from the third
week 37 times. The fourth week, study participants from the social cognitive theory-
based health information group viewed the webinars from the fourth week 47 times. The
non- social cognitive theory-based health information group viewed the webinars from
the third week 54 times (see Table 8).
Table 8
Pre-Recorded Narrated Webinar Views
Study Week
SCT Group Number of Views
Non-SCT Group Number of Views
Week 1
6
3
Week 2
10
54
Week 3
38
37
Week 4
47
54
There were four discrepancies in data collection from the plan presented in
chapter three. First, although study participants were enrolling in my study at a steady
pace from the Walden University online participation pool and the private school in
Chicago, IL., a few months into the study, enrollment in the study began to ebb. As of
September 2018, momentum in study enrollment began to reduce from five to ten
participants a day to one or two study participants a day. Although study enrollment was
steady, it would take a significant amount of time to achieve a minimum of sixty-eight
participants. Therefore, after discussing this challenge with the committee chair
additional internet sites were reviewed that could offer access to research participants.
The following terms were utilized while conducting an internet search “research pool,”

121
“research panel,” “research participation pools,” “human subjects pool,” “buy research
subjects,” recruit participants,” “online panels,” “online research panels,” find survey
participants,” and “find survey participants online.” Numerous websites were contacted
and analyzed, and Findparticipants.com and Researchandme.com were identified as ideal
websites. These websites were selected for three reasons. First, these websites offered
access to research participants for a reasonable fee. Second, there was no requirement to
compensate study participants. Third, metrics were offered that allowed me to track the
marketing outreach or recruitment of the recruiting ad for my study. I demonstrated the
websites to my committee chair and secured approval to submit a request to the IRB.
September 6th 2018, I contacted Walden University’s IRB and submitted a “request for
change in procedures” form. The Walden University IRB approved the request
September 18, 2018.
The second discrepancy in data collection was the lack of post-test completion.
As study participants approached the end of the four-week study, a reminder was e-
mailed during the third week of the study. The reminder thanked study participants for
completing the third week of the study and reminded them that the following week would
be the fourth and final week of the study. The message also urged study participants to
complete the post-test after reviewing the information for the fourth week of the study.
Weekly reminder e-mails were sent to study participants that completed the four-
week study for one month after study participants completed the study. However, only
two or three study participants completed the post-test every week after numerous
reminders. Therefore, the frequency of the reminders was increased from once per week

122
to three times per week. This increased the rate of post-test completion. Before, two to
three study participants would complete the post-test every week. After increasing the
frequency of the reminder e-mails, five to 10 people would complete the post-test.
After numerous reminders to complete the post-test were sent to study
participants that had completed the four-week study, I received feedback from three
participants that stated that they were unable to open the health information that had been
sent over the last four weeks. These study participants stated that this was the reason they
refused to complete the post-test. Therefore, I created PDF versions of both the social
cognitive theory and non-social cognitive theory versions of the health information. I sent
the PDF versions of the health information to the three study participants. Also, as a
preventative measure and to ensure that this problem didn’t prevent other study
participants from viewing the health information or completing the post-test, the PDF
versions of the health information was sent to all study participants that completed the
study as well. In addition, any new study participants were sent the PDF version of the
health information along with the originally scheduled narrated versions of the health
information and PowerPoint presentations.
The third discrepancy in data collection was that although previous research had
indicated that those that are overweight and obese have a higher than normal BMI and
therefore have a higher chance of being food addicted only 40.5% of study participants
met the criteria for being food addicted according to the Yale Food Addiction Scale.
However, food addiction research is a new and burgeoning field and the Yale Food
Addiction Scale is a relatively new instrument used to formally test and confirm food

123
addiction. New discoveries and insights into food addiction and the Yale Food Addiction
scale are frequently being identified. For example, one of the founders and creators of the
Yale Food Addiction Scale, Dr. Ashley Gearhardt and her team recently published a
study earlier this year where she observed a smaller than anticipated percentage (38.6%)
of study participants (n = 17, N = 44) that met the criteria for food addiction according to
the Yale Food Addiction Scale (Schulte, Sonneville, & Gearhardt, 2019). This is quite
remarkable given the resources that her research team had available to recruit a larger
sample size. Another recent study conducted by Gerhardt and her research team has
emerged with similar findings. Schulte, Jacques-Tiura, Gearhardt, and Naar (2018)
recruited a larger sample size to study the effect of processed foods on food addiction and
utilized the Yale Food Addiction Scale. Even with a larger sample size (n = 501), only
14.6% percent of their study participants met the criteria for food addiction.
The fourth discrepancy in data collection was multiple pre-test completions by the
same person. This posed a challenge for two reasons. First, if unaddressed, the same
study participant would receive health information for both the social cognitive theory-
based health information group and the non- social cognitive theory-based health
information group. This error would have inflated the final total of recruited study
participants and therefore skew the study results. However, the data was consistently
analyzed and cleaned to prevent duplicate entries. Also, as mentioned in chapter two,
study participants were prohibited from skipping survey questions to prevent the problem
of missing data in the final study. Finally, there were no adverse events related to sharing
the social cognitive theory-based health information.

124
Descriptive and Demographic Characteristics of the Sample
Descriptive and demographic characteristics of the sample include the following.
Eighty-four participants completed the four-week study, pre-test, and post-test. The
ethnicity of the study participants was as follows: Asian/Pacific Islander, 2.4% (n = 2),
Black or African American, 21.4% (n = 18), Hispanic, 7.1% (n = 6), Mixed, black/white
1.2% (n = 1), Native Hawaiian, Caucasian, Asian 1.2% (n = 1), and White/Caucasian
66,7% (n = 56) (See Table 9). This sample represents the population of interest in that all
study participants were female, diverse in composition, literate, willing to complete a
survey, and willing to participate in an eating behaviors study.
Table 9
Frequency and Percent Statistics of Study Participant Ethnicity
Demographic Characteristics
Frequency (n)
Percent (%)
Gender
Asian/Pacific Islander
2
2.4%
Black or African American
18
21.4%
Hispanic
6
7.1
Mixed, black/white
1
1.2 %
Native Hawaiian, Caucasian, Asian
1
1.2 %
White/Caucasian
56
66.7 %
Total
84
100%
Most study participants completed graduate school. The education level of study
participants are as follows: Graduated from high school, 4.8% (n = 4), One year of
college, 2.4% (n = 2), Two years of college, 8.3% (n = 7), Three years of college,
10.7%(n = 9), Graduated from college, 27.4% (n = 23), Some graduate school, 14.3% (n
= 12), Completed graduate school, 32.1% (n = 27). The table provides a summary below
(see Table 10).

125
Table 10
Education Level Descriptive Statistics
Education Level
Frequency
Percent
Valid
Percent
Cumulative
Percent
1 year of college
2
2.4
2.4
2.4
2 years of college
7
8.3
8.3
10.7
3 years of college
9
10.7
10.7
21.4
Completed graduate school
27
32.1
32.1
53.6
Graduated from college
23
27.4
27.4
81.0
Graduated from high school
4
4.8
4.8
85.7
Some graduate school
12
14.3
14.3
100.0
Total
84
100.0
100.0
Study participants were also asked if they had ever received a mental health
diagnosis. Fifty-six percent of study participants answered “Yes,” and forty-four percent
of study participants answered “No” to this question.
There were improvements to study participants’ food addiction symptoms as a
whole group. Almost 60% (n = 50) of the study participants experienced a decrease in
food addiction symptoms. Twenty-two percent (n = 19) of study participants experienced
an increase in food addiction symptoms. Almost eighteen percent (n = 15) of study
participants experienced no change in food addiction symptoms (see table 9).
Overall group food addiction scores and symptom count scores improved. Almost
60% of all study participants experienced a decrease in both food addiction scores and
symptom count scores. This change includes sixty percent of study participants that
experienced a decrease in symptom count (n = 50) and 56% of study participants

126
experienced a decrease in food addiction (n = 47). The table below provides a summary
(see Table 11).
Table 11
Overall Food Addiction & Food Addiction Symptom Count Scores
Change to
Food Addiction
Symptoms
Frequency
Symptom
Count Score
Percent
Symptom
Count Score
Frequency
Food Addiction
Score
Percent
Food
Addiction
Score
Decrease
50
59.5%
47
56%
Increase
19
22.6%
18
21.4%
No Change
15
17.9%
19
22.6
Total
84
100%
84
100%
Overall, study participants experienced an improvement and decrease in their
BMI levels. The non- social cognitive theory-based health information group saw the
greatest improvement to their BMI levels 61.9% (n = 26). The social cognitive theory-
based health information group also saw an improvement and decrease to their BMI
levels 40.5% (n = 17). Some members of the social cognitive theory-based health
information group saw an increase and decline to their BMI levels (33.3%, n = 14). The
same decline was observed for the non-social cognitive theory-based health information
group (28.6%, n = 12). Almost 26% (n = 11) of study participants in the social cognitive
theory-based health information group experienced no change compared to 9.5% (n = 4)
of the members of the non- social cognitive theory-based health information group. A
brief summary is displayed in the table below (see Table 12).

127
Table 12
Changes to BMI by Health Information Group
BMI Change
SCT Health
Information Group
NSCT Health
Information Group
BMI Increased
33.3% (n = 14)
28.6% (n = 12)
BMI Decreased
40.5% (n = 17)
61.9% (n = 26)
No Change
26.2% (n = 11)
9.5% (n = 4)
Total
100% (n = 42)
100% (n = 42)
The health information was administered as planned. There were three
unanticipated challenges. However, these challenges did not prevent implementing the
plans as described in chapter three. The first unanticipated challenge to delivering the
health information was the e-mail containing the attached health information was rejected
and listed as undeliverable to study participant’s e-mail addresses. This rejection was due
to the large size of the attached health information file which was in a PowerPoint format.
Study participants’ e-mail providers interpreted the large file size as a virus and therefore
blocked the file. This was addressed by uploading the health information to Dropbox and
creating a link that the study participant could select when they opened the researcher’s e-
mail. Once participants opened the Dropbox link, the PowerPoint file containing the
health information opened.
The third and final unanticipated challenge was at the conclusion of the four-week
study. A small number of participants stated that they were unable to open the health
information sent and were afraid to open the link to the narrated version of the health

128
information and did not complete the post-test. This feedback was addressed by
converting all health information into PDF files. The PDF files were sent to the study
participants that stated they were unable to open the Dropbox link. All participants that
had completed the post-test were contacted and informed that as a courtesy, the PDF
version of the health information was being provided. Also, all participants that had
completed the pre-test, but had not completed the post-test were contacted and provided
the PDF version of the files as a courtesy and to encourage post-test completion.
Results
The research questions and hypothesis were as follows:
RQ1. What is the extent of the difference in food addiction post-test scores (while
controlling for any differences at pre-test) as measured by the Yale Food Addiction Scale,
among overweight and obese women who receive Social Cognitive Theory-based health
information compared to overweight and obese women who receive non-Social Cognitive
based health information?
H01. When comparing the impact of social cognitive theory-based health
information with non- social cognitive theory -based health information presented to
overweight or obese women, there is no significant difference in food addiction posttest
scores (while controlling for differences in pretest scores) as measured by the Yale Food
Addiction Scale.
HA1. When comparing the impact of social cognitive theory -based health
information with non- social cognitive theory -based health information presented to
overweight or obese women, there is a significant difference in food addiction posttest

129
scores (while controlling for differences in pre-test scores) as measured by the Yale Food
Addiction Scale.
RQ2. What effect does social cognitive theory-based health information have on
symptom count post-test scores, as measured by the Yale Food Addiction Scale, among
obese and overweight women compared to obese and overweight women who receive the
non-Social Cognitive based health information?
H02. When comparing the impact of social cognitive theory -based health
information with non- social cognitive theory-based health information presented to
overweight or obese women, there is no significant difference in symptom count post-test
scores as measured by the Yale Food Addiction Scale.
HA2. When comparing the impact of social cognitive theory-based health
information with non- social cognitive theory -based health information presented to
overweight or obese women, there is a significant difference in symptom count post-test
scores as measured by the Yale Food Addiction Scale.
I explored the first research question using ANCOVA because I wished to
examine any potential changes in food addiction scores as measured by the scores on the
Yale Food Addiction scale (see Appendix A). The pre-test was used as a covariate to
determine if there were any significant differences (if any) between the two comparison
groups and the effectiveness of the social cognitive theory-based health information. The
dependent variable for this analysis was the food addiction score. The dependent variable
food addiction score was calculated and was comprised of a combination of the food
symptom count score and the clinical significance and impairment score. If the food

130
addiction symptom count was greater than or equal to three or more and the participant
indicated by answering yes, that they experienced at least one of the two clinical
significance and impairment symptoms, then the participant met the diagnostic criteria
for food addiction (Gearhardt et al., 2012). For ease of entering data into SPSS, the two
scores were combined into one number (Gearhardt et al, 2012). The scores for both the
social cognitive theory -based health information group and the non- social cognitive
theory -based health information group were then entered into SPSS to calculate the food
addiction score. The following tables review the descriptive statistics of both groups
(range, median, mode, etc..) for the food addiction and symptom count scores (see Table
2, Table 3, Table 4, Table 5, and Table 6).
The independent variable for the first research question is group status; either the
group having received social cognitive theory -based health information (social cognitive
theory group) or not received (non- social cognitive theory group). One group of study
participants–the social cognitive theory-based health information group–received weekly
presentations that disseminated health information that modeled key facets of social
cognitive theory, such as self-efficacy, outcome expectations, observational learning,
incentive motivation, facilitation, and self-regulation. The non- social cognitive theory -
based health information group received weekly presentations that disseminated health
information and did not model any facets of social cognitive theory.
Statistical Assumptions
All the data from the dependent variables, pre-test and post-test food addiction
scores and pre-test and post-test food symptom count, were reviewed and analyzed for

131
missing data and univariate outliers before assessing assumptions. There was no missing
data or cases because I designed the survey in SurveyMonkey to prevent study
participants from skipping or missing questions. Raw scores were converted into z-scores
and I compared scores to the value of +/- 3.29, p < .001 (Tabachnick & Fidell, 2007).
Any z-scores that exceeded 3.29 would be considered outliers because these scores would
be three standard deviations away from the mean. I reviewed the distributions and found
no univariate outliers.
Normality
Basic parametric assumptions were reviewed before analyzing the research
questions. This approach entailed testing assumptions of normality and homogeneity of
variance of the dependent variables. Distributions were tested to confirm normal
distribution by conducting an analysis using the descriptives and explore function in
SPSS 25. An evaluation of the Kolmogorov-Smirnov and Shapiro-Wilk found statistical
significance for all dependent variables. Therefore, the assumption of normality has been
violated and the distributions can be assumed to not be normally distributed. Table 13
and Table 14 displays the skewness and kurtosis statistics of all dependent variables.
Table 13
Summary of Descriptive Statistics Symptom Count Scores
Symptom
Count
N
M
Skew.
Kurtosis
S D
Kolmogorov
- Smirnov
Shapiro-
Wilk
Pre-Test
84
4.12
-.358
-.414
1.609
.000
.003
Post-Test
84
3.27
-.354
-.651
1.752
.000
.001
S D = Standard Deviation
132
Table 14
Summary of Descriptive Statistics Food Addiction Scores
Food
Addiction
N
M
Skew.
Kurtosis
S D
Kolmogorov
- Smirnov
Shapiro-
Wilk
Pre-Test
84
4.58
-.152
-.443
1.915
.001
.042
Post-Test
84
3.62
.522
-.506
2.094
.000
.001
S D = Standard Deviation
To test further, Paired T-Test results were also tested for normality. Figure 1
displays that skewness and kurtosis statistics of the difference of the symptom count
scores. Although the score indicates statistical significance, the normal Q -Q Plot of
Difference indicates that assumption of normality is satisfied. See Table 15 below and
Histograms and plots of the analysis are demonstrated on Figure 1 to Figure 11.
Table 15
Assumption of Normality Test
N
M
Skewness
Kurtosis
SD
Kolmogorov
- Smirnov
Shapiro-
Wilk
Difference
in Symptom
Count
Scores
84
.85
-.052
-.496
1.840
.000
.013
M = Mean
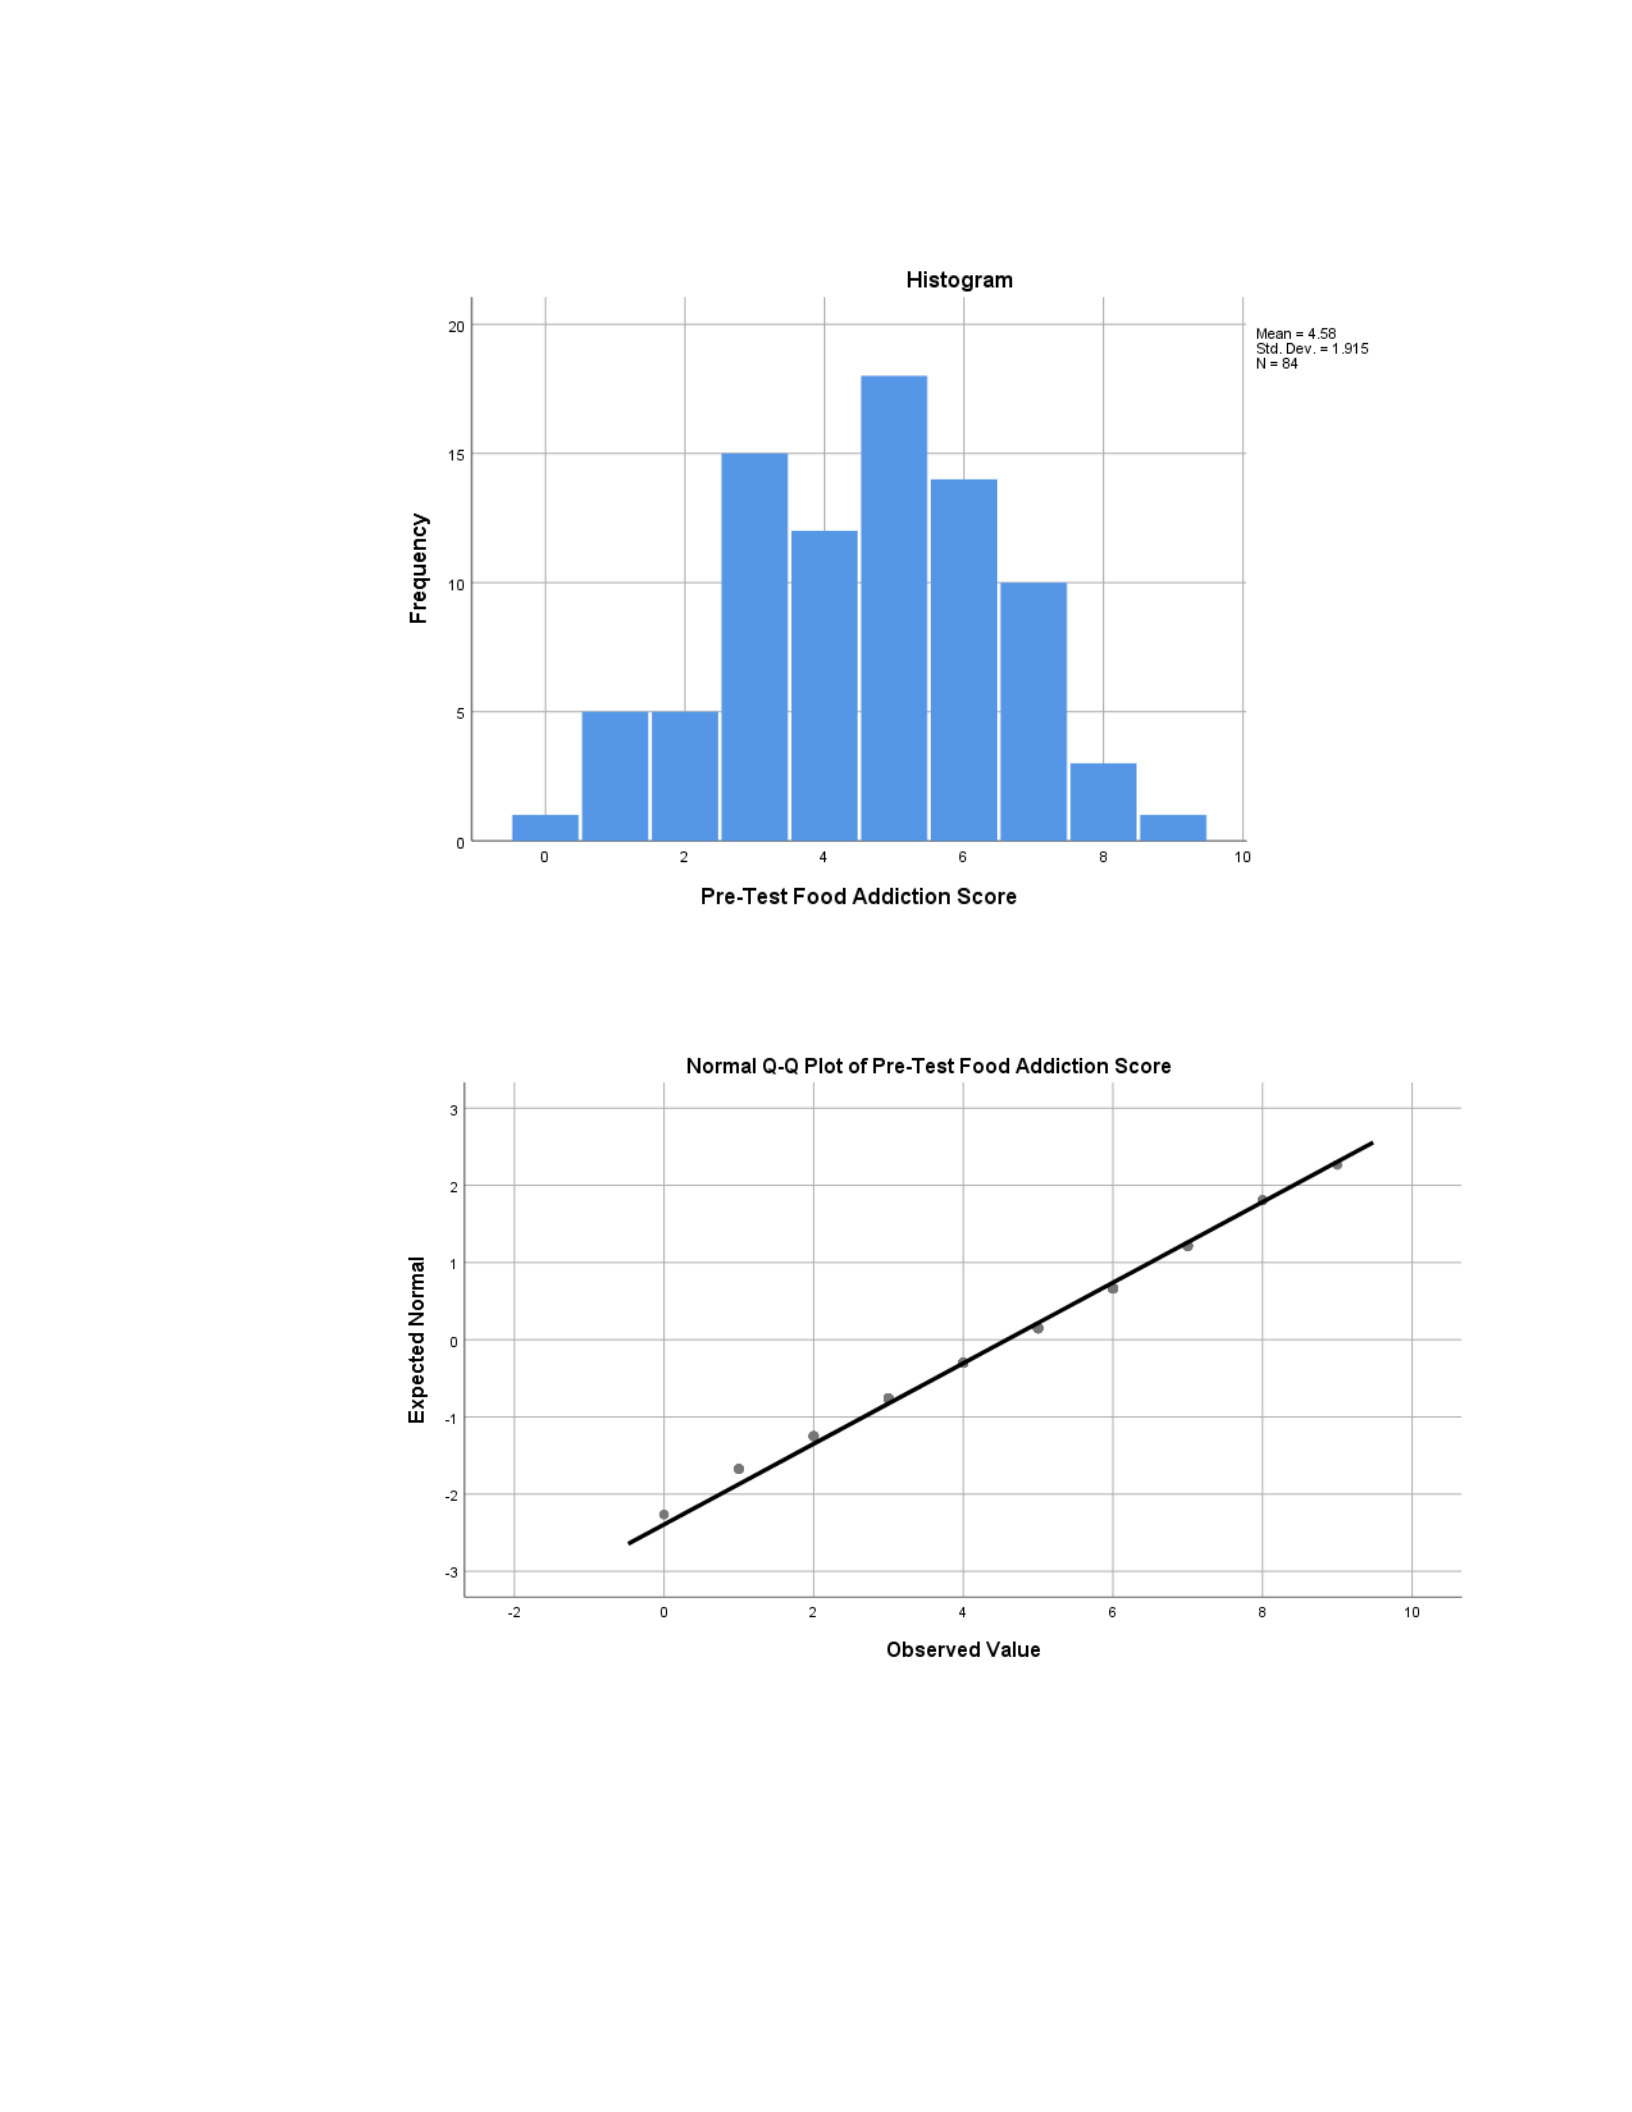
133
Figure 1. Histogram.
Figure 2. Normal Q-Q plot.
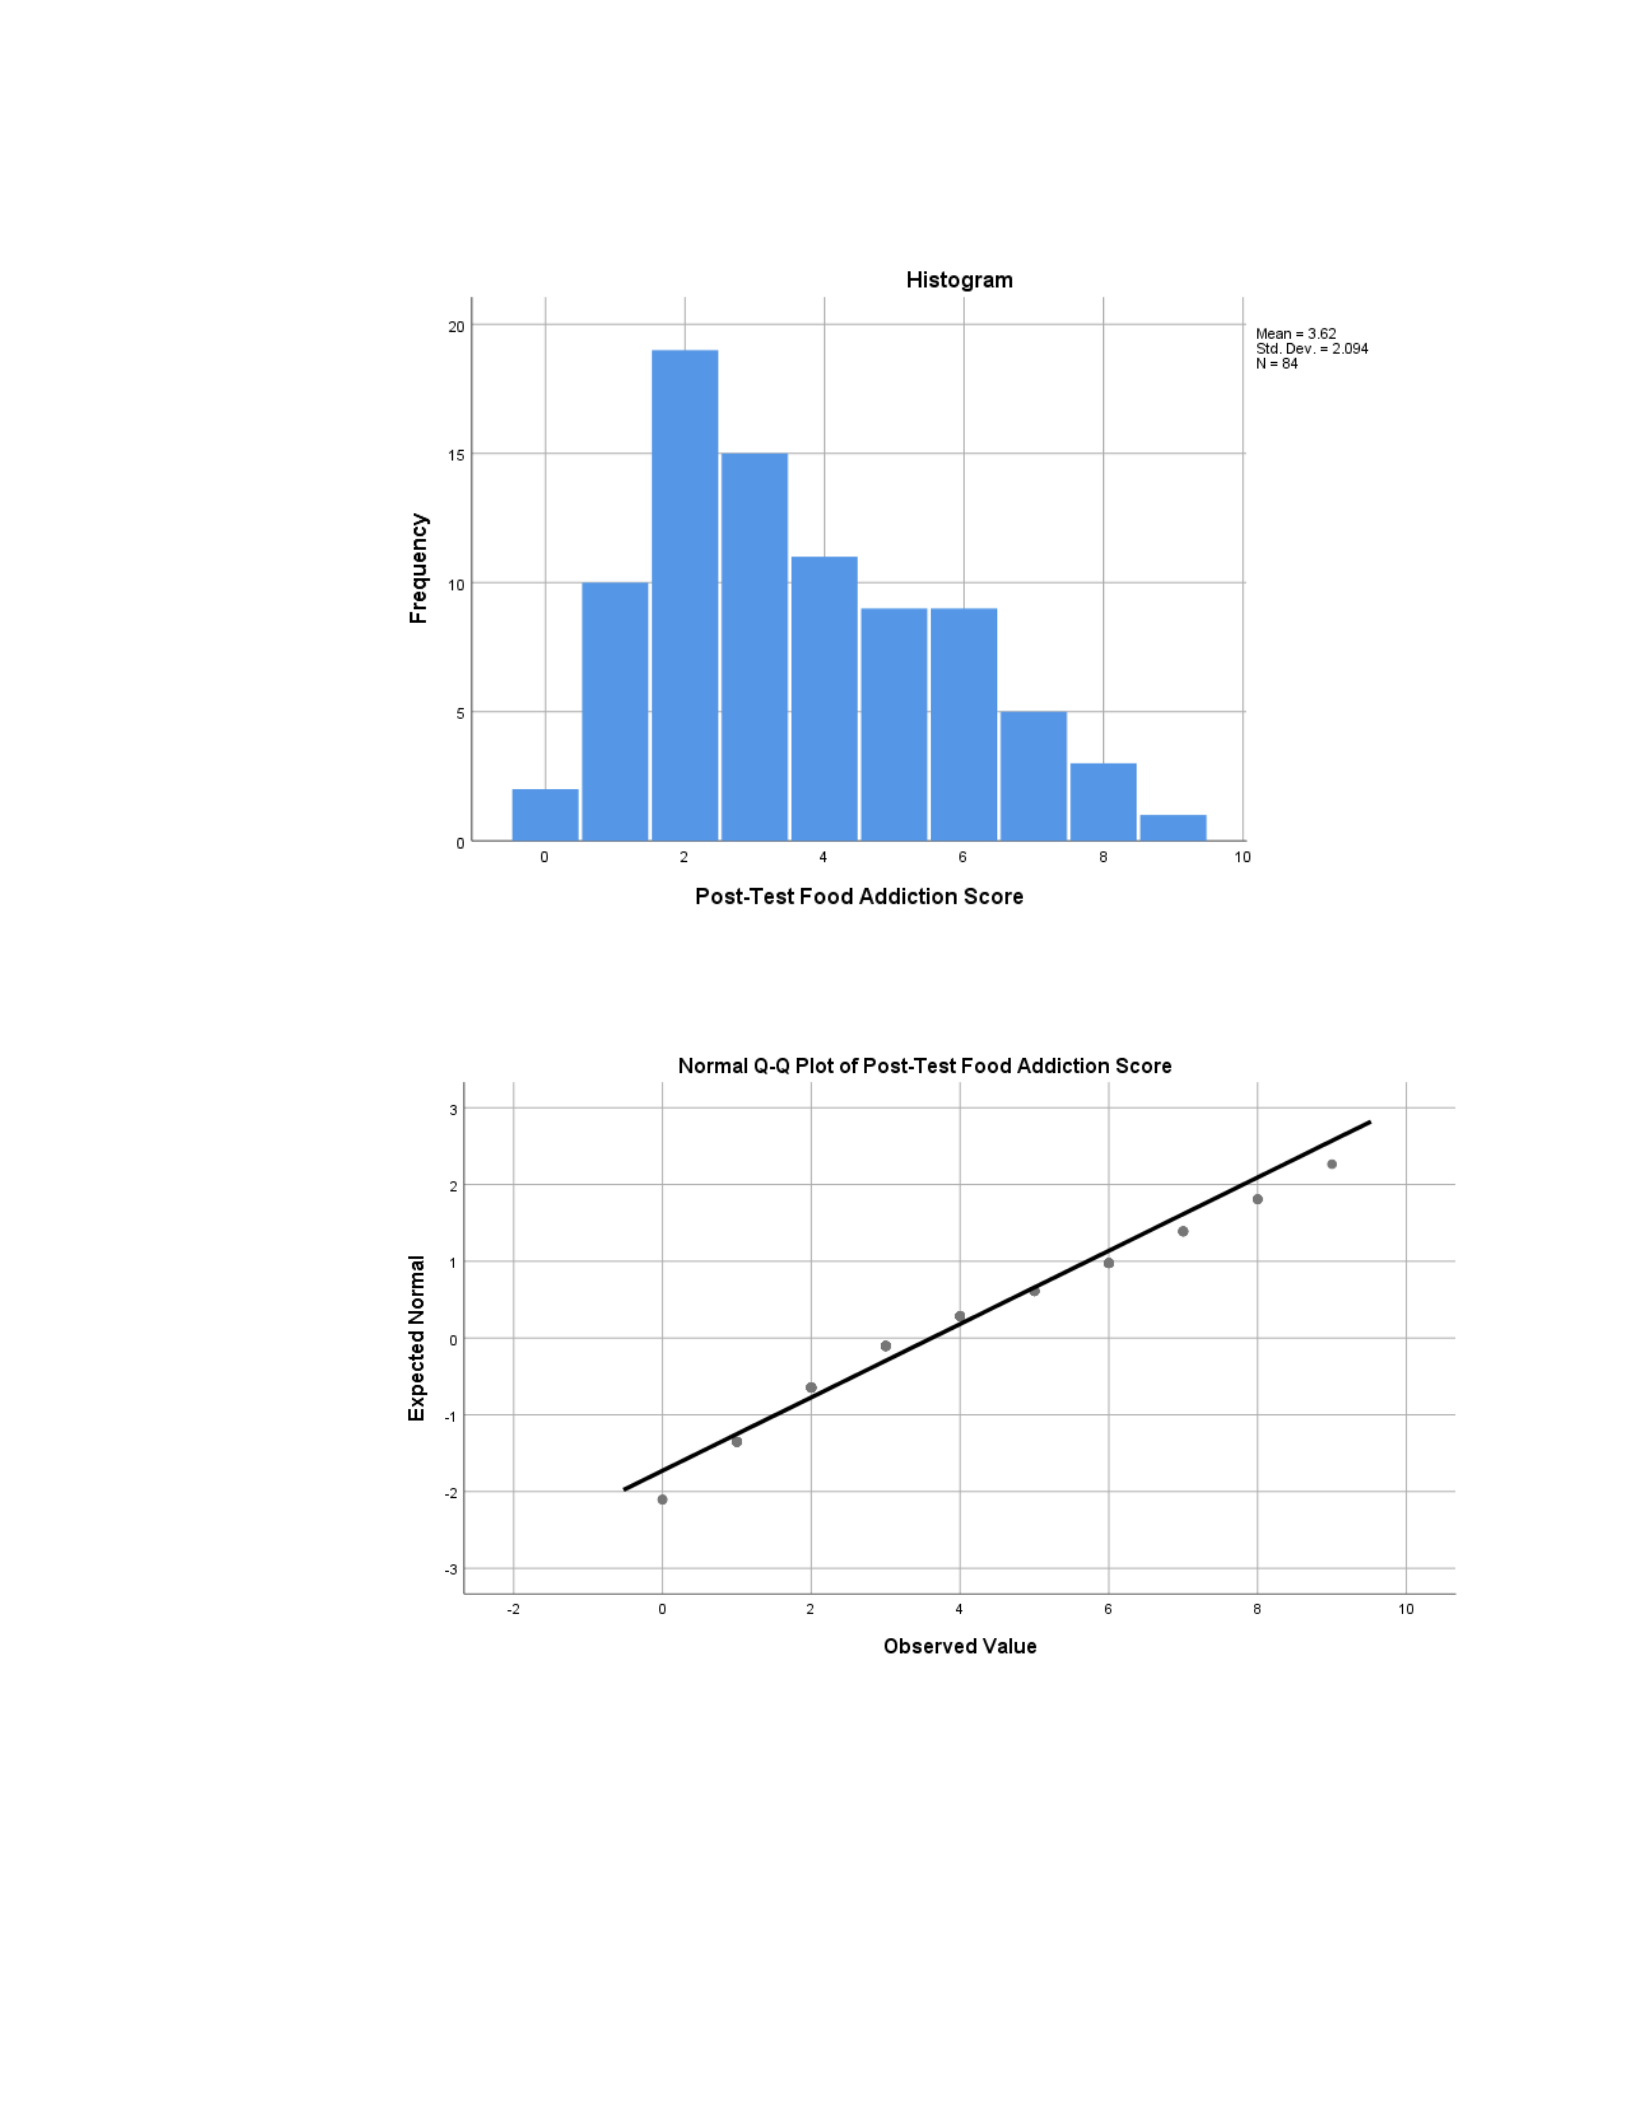
134
Figure 3. Histogram.
Figure 4. Normal Q-Q plot.
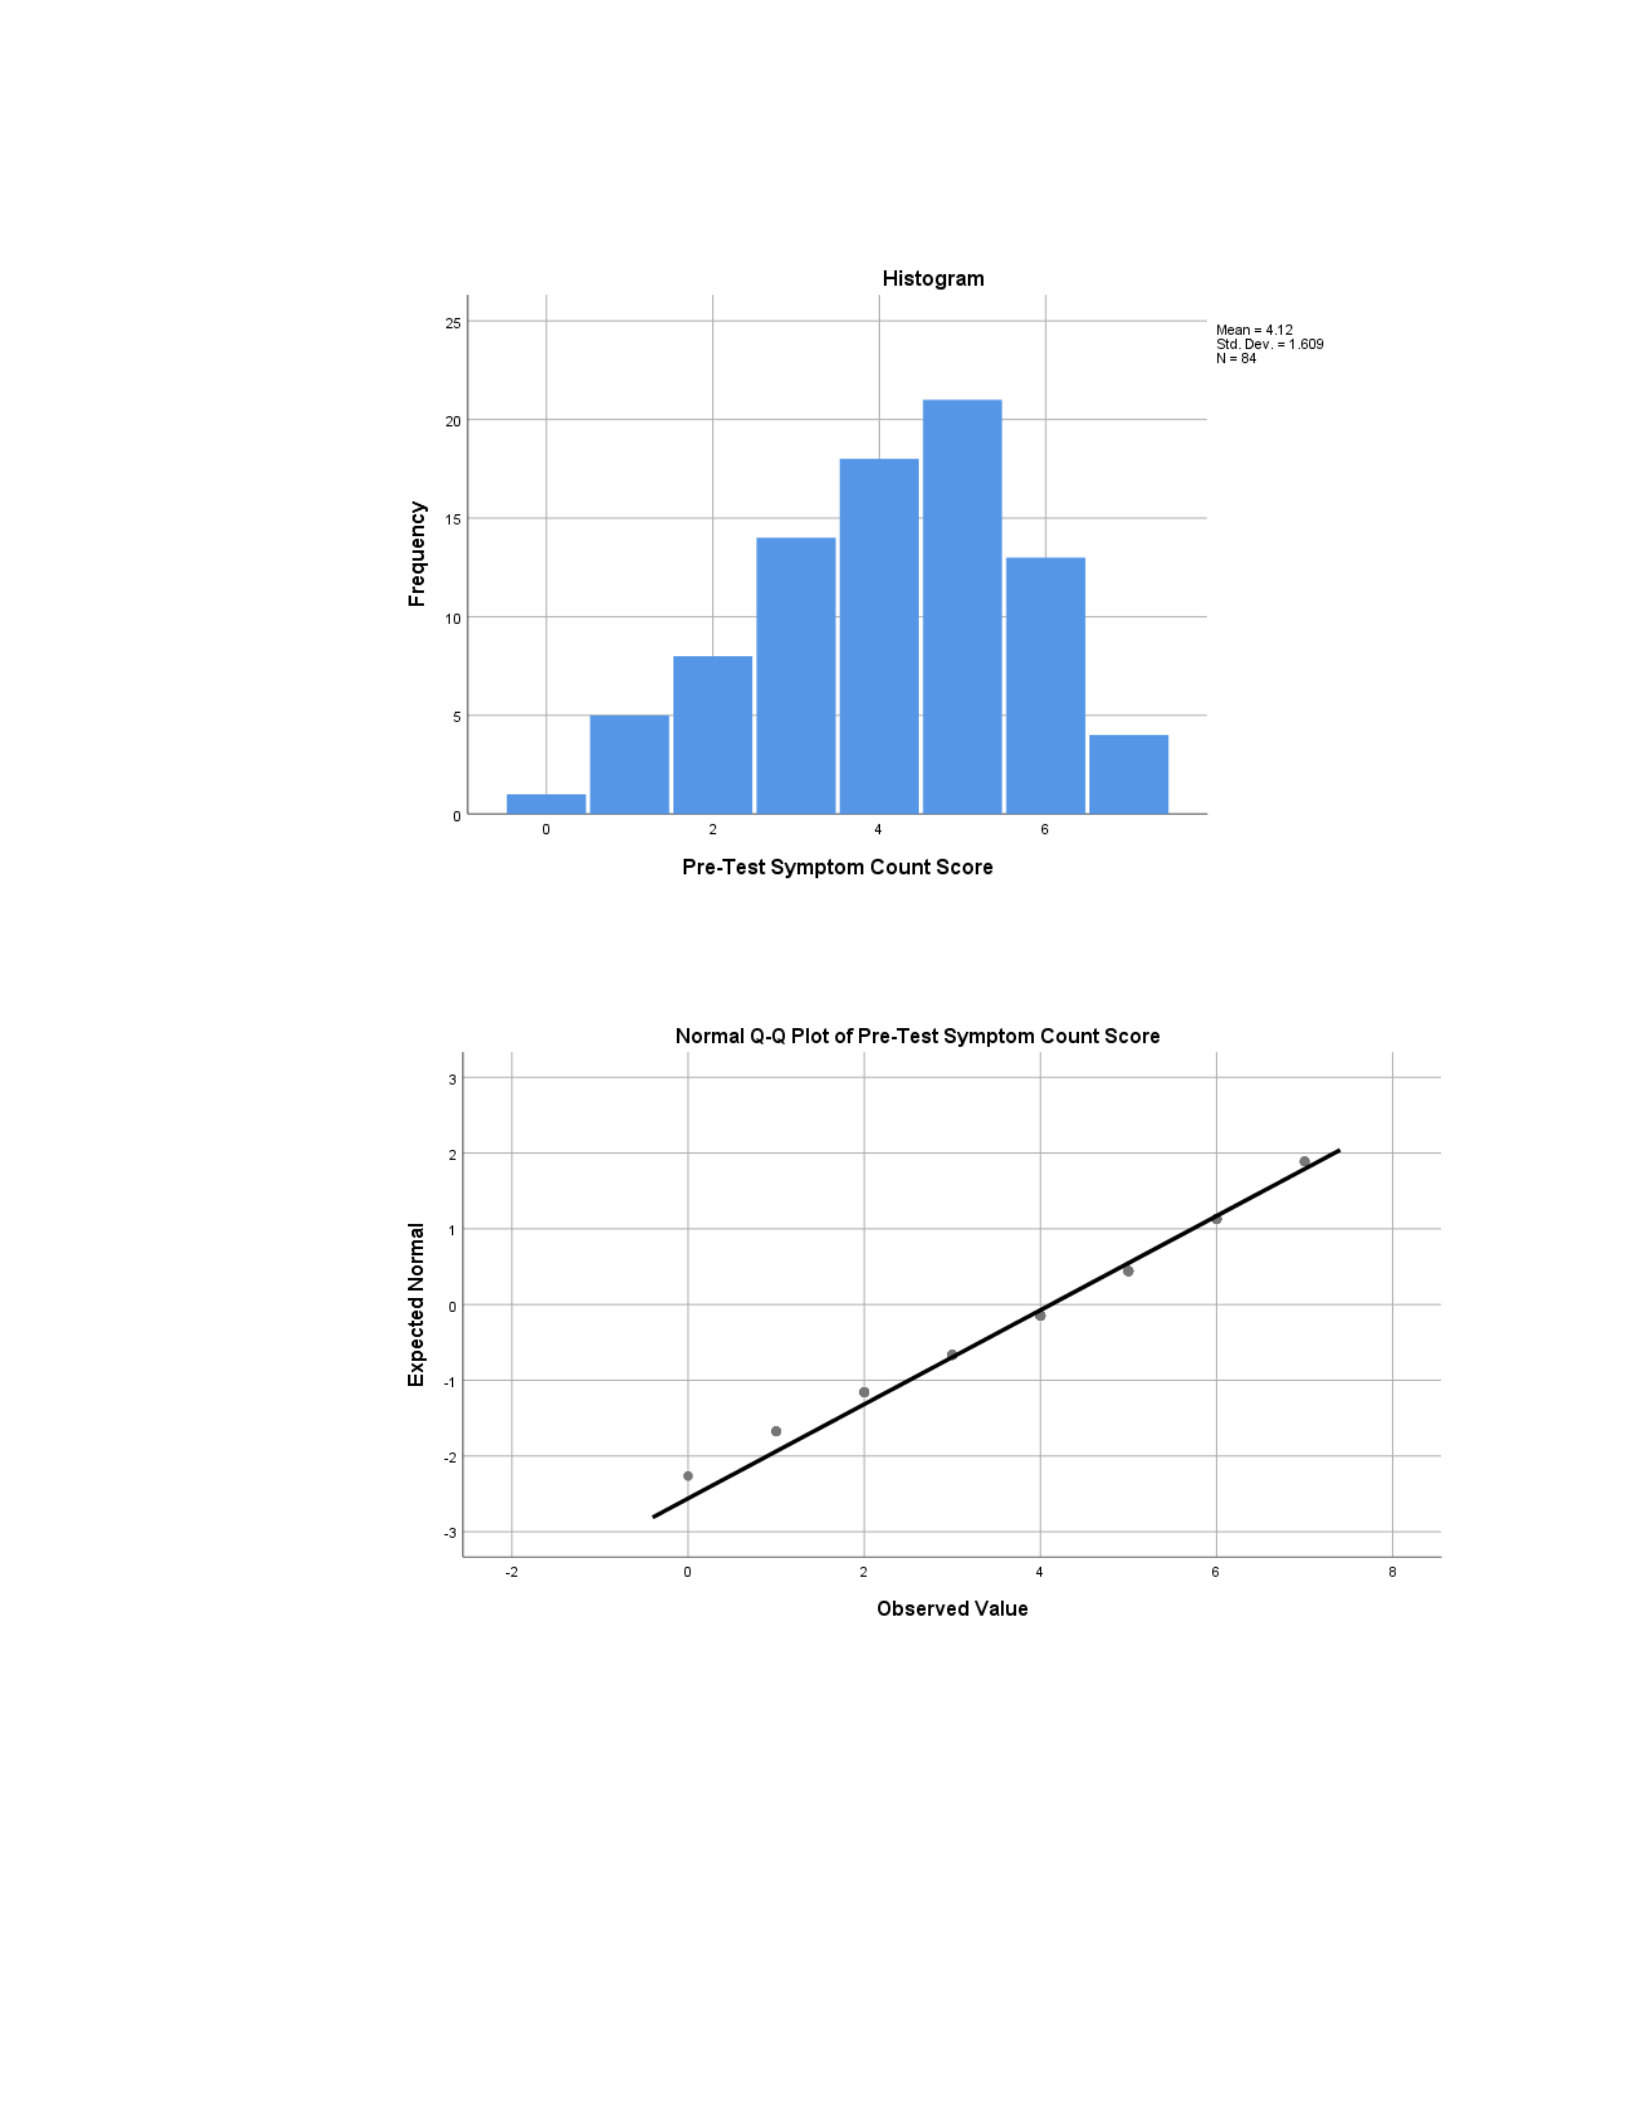
135
Figure 5. Histogram.
Figure 6. Normal Q-Q plot.
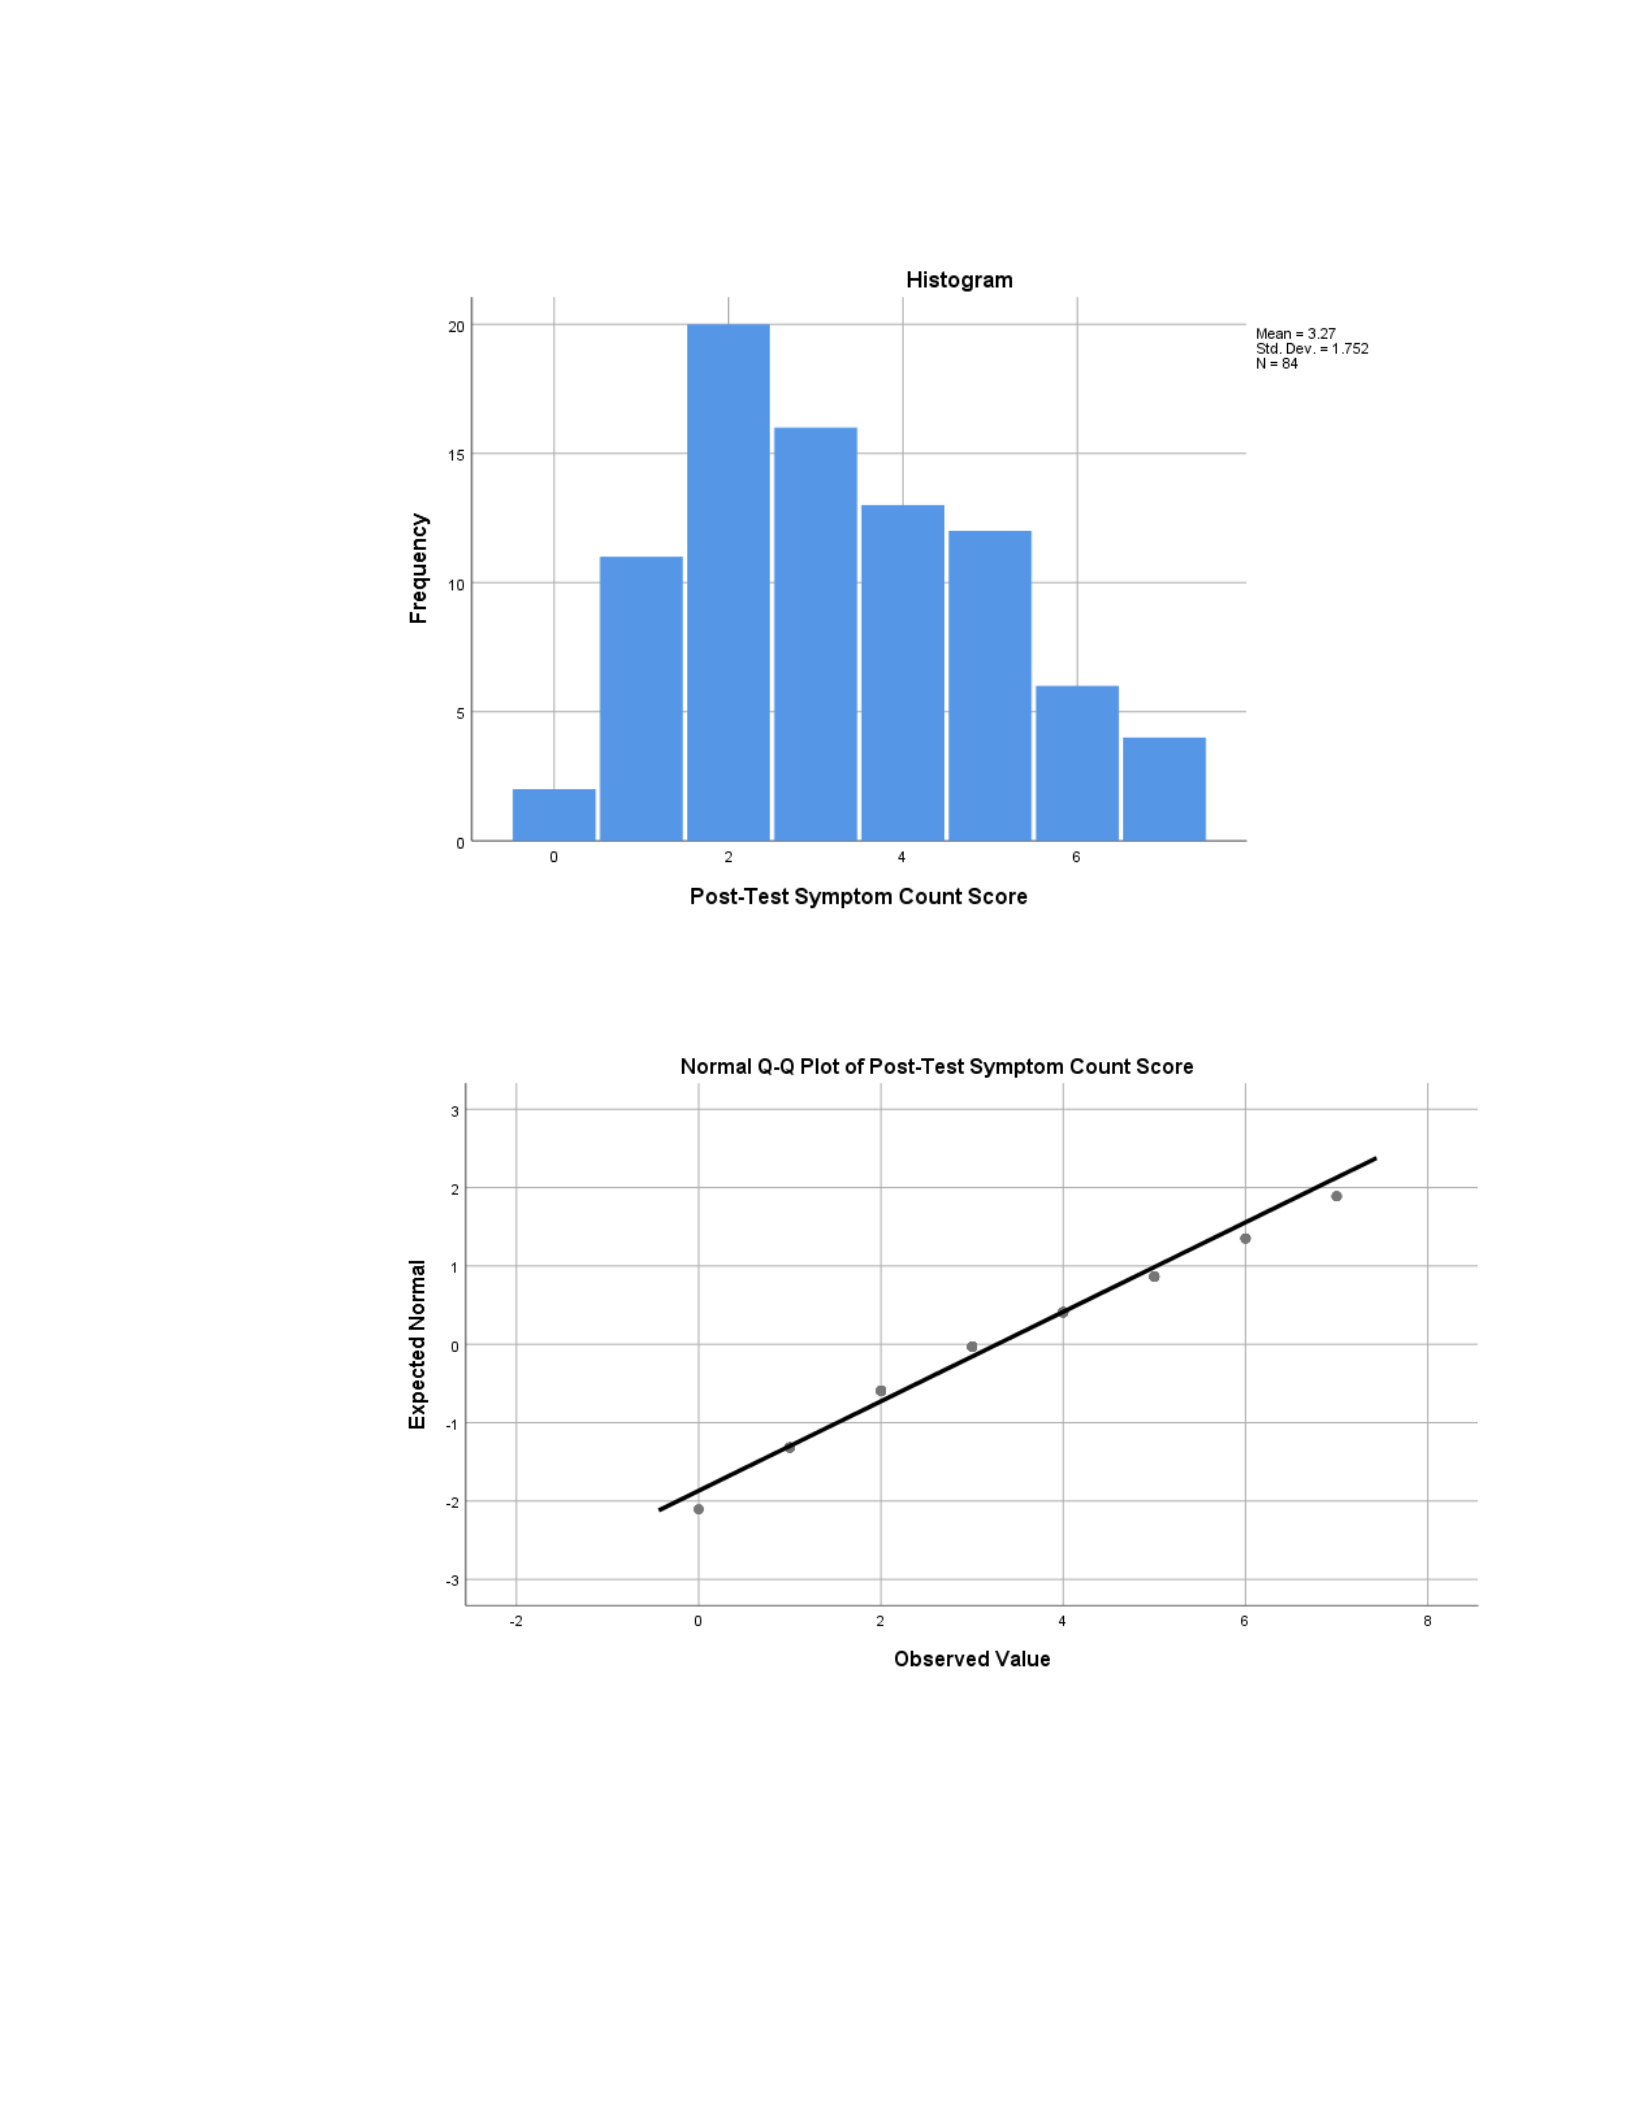
136
Figure 7. Histogram.
Figure 8. Normal Q-Q plot.
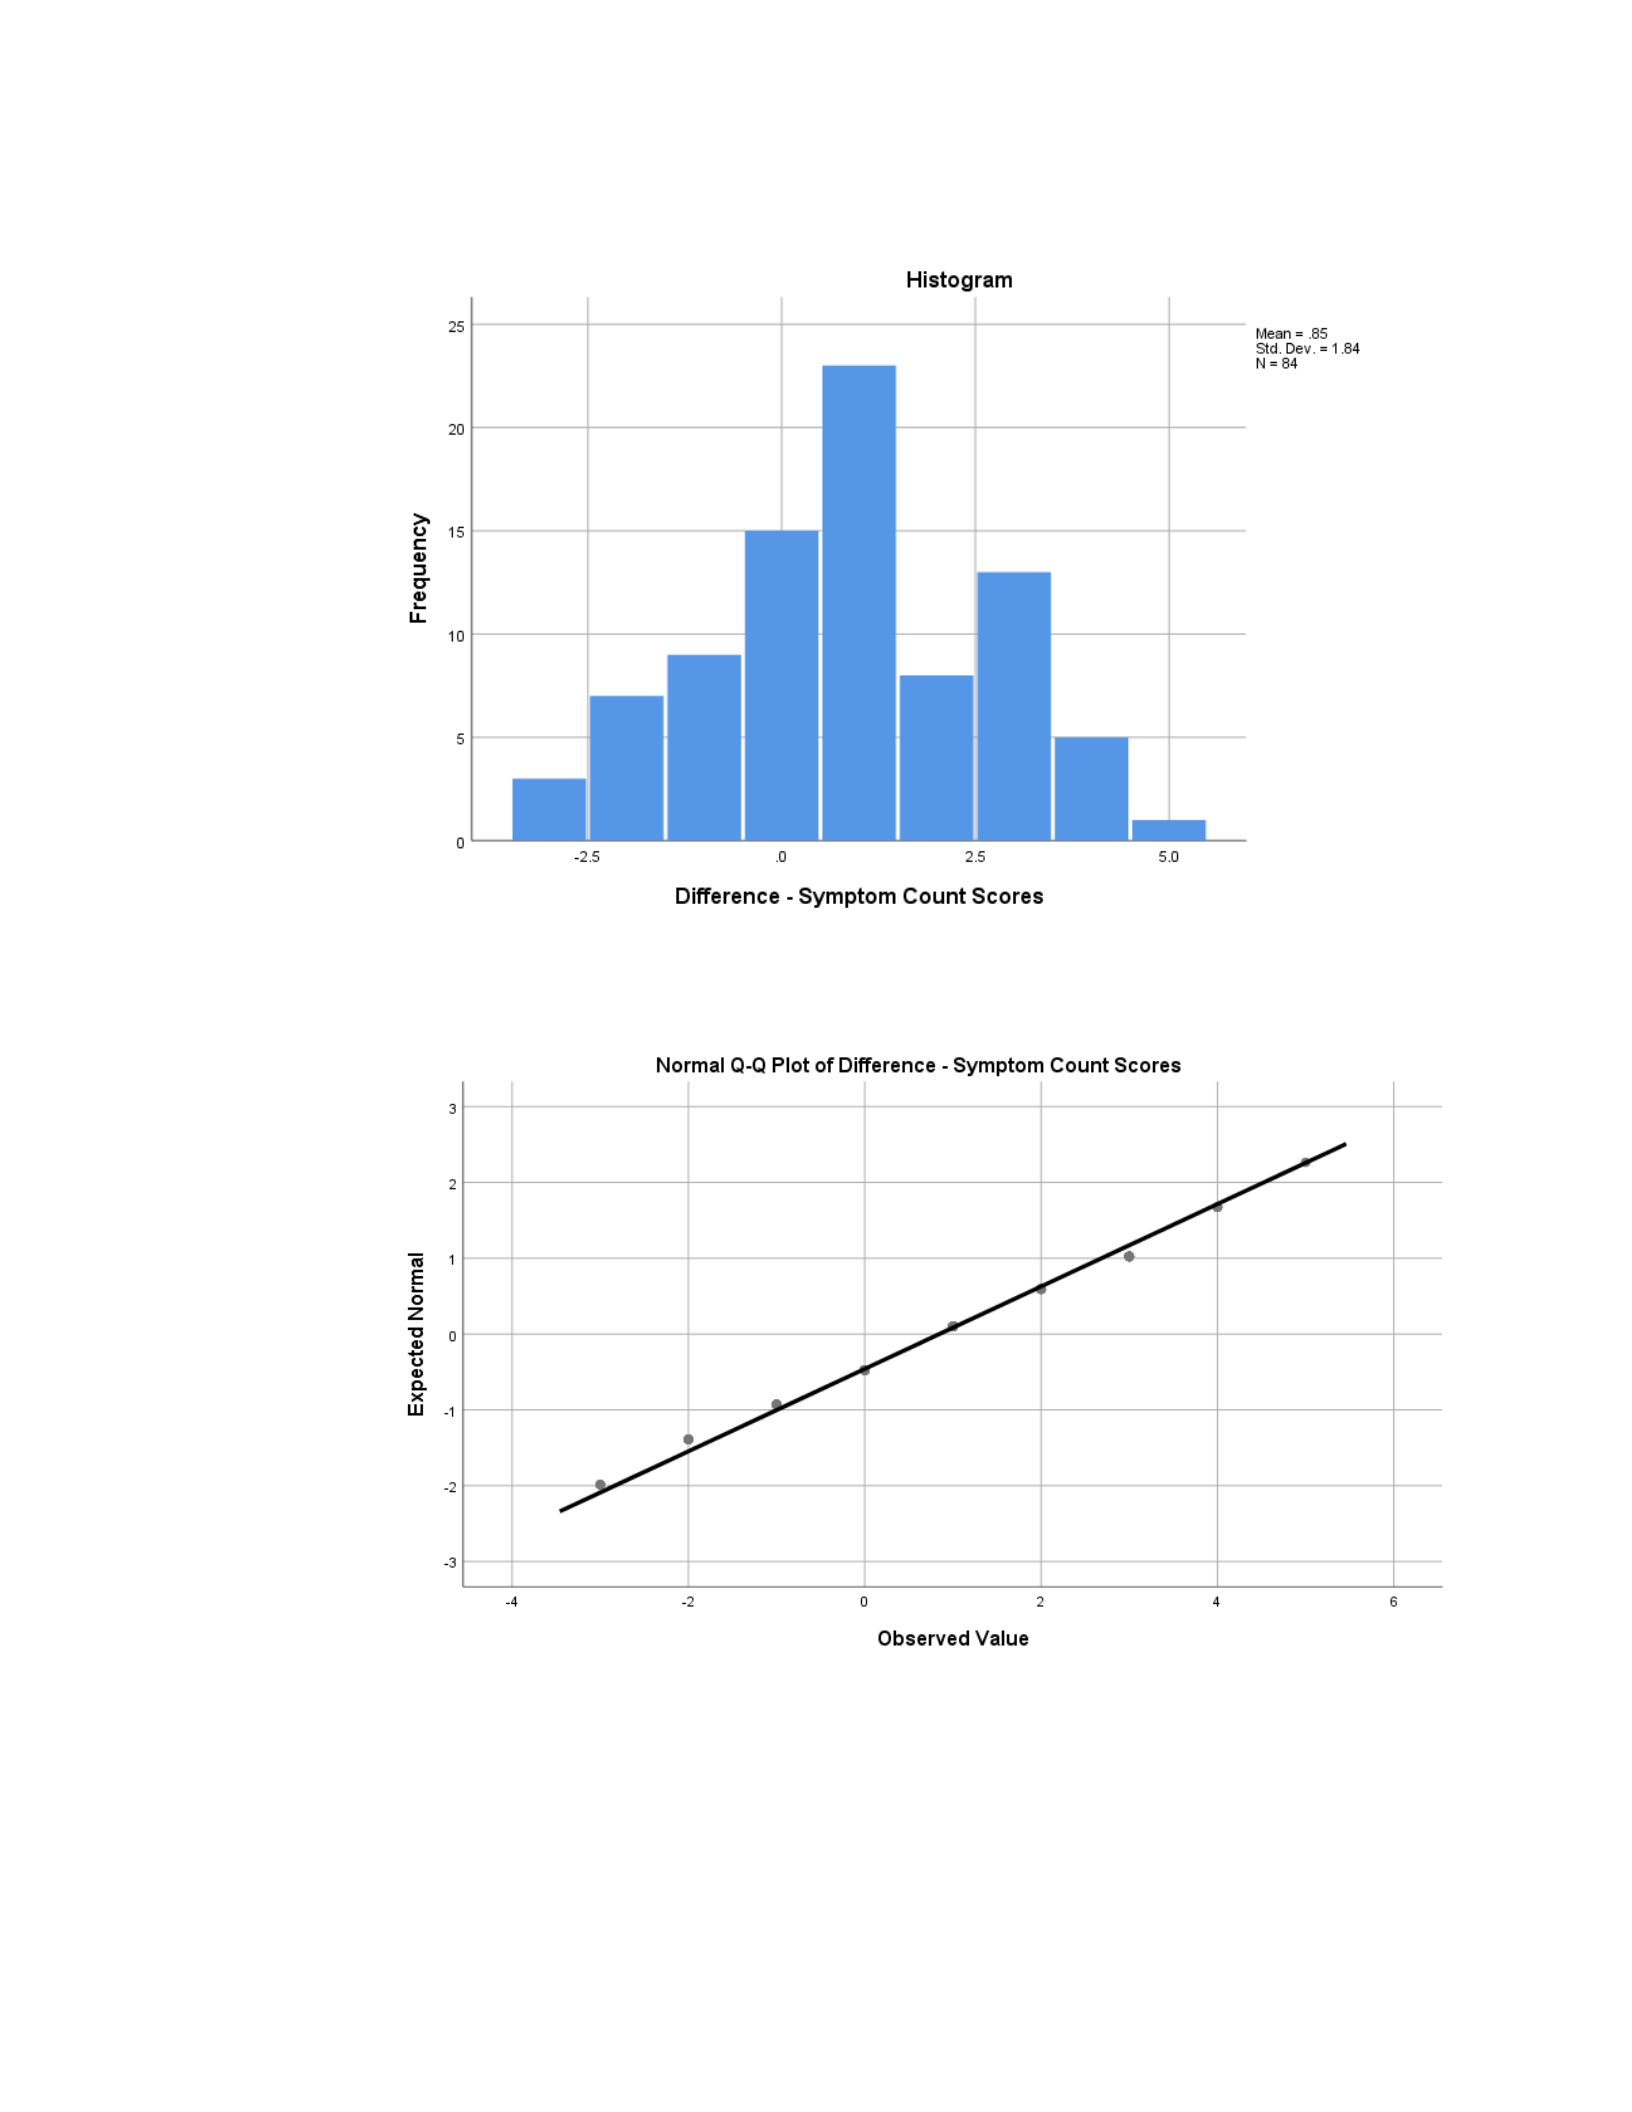
137
Figure 9. Histogram.
Figure 10. Normal Q-Q plot.
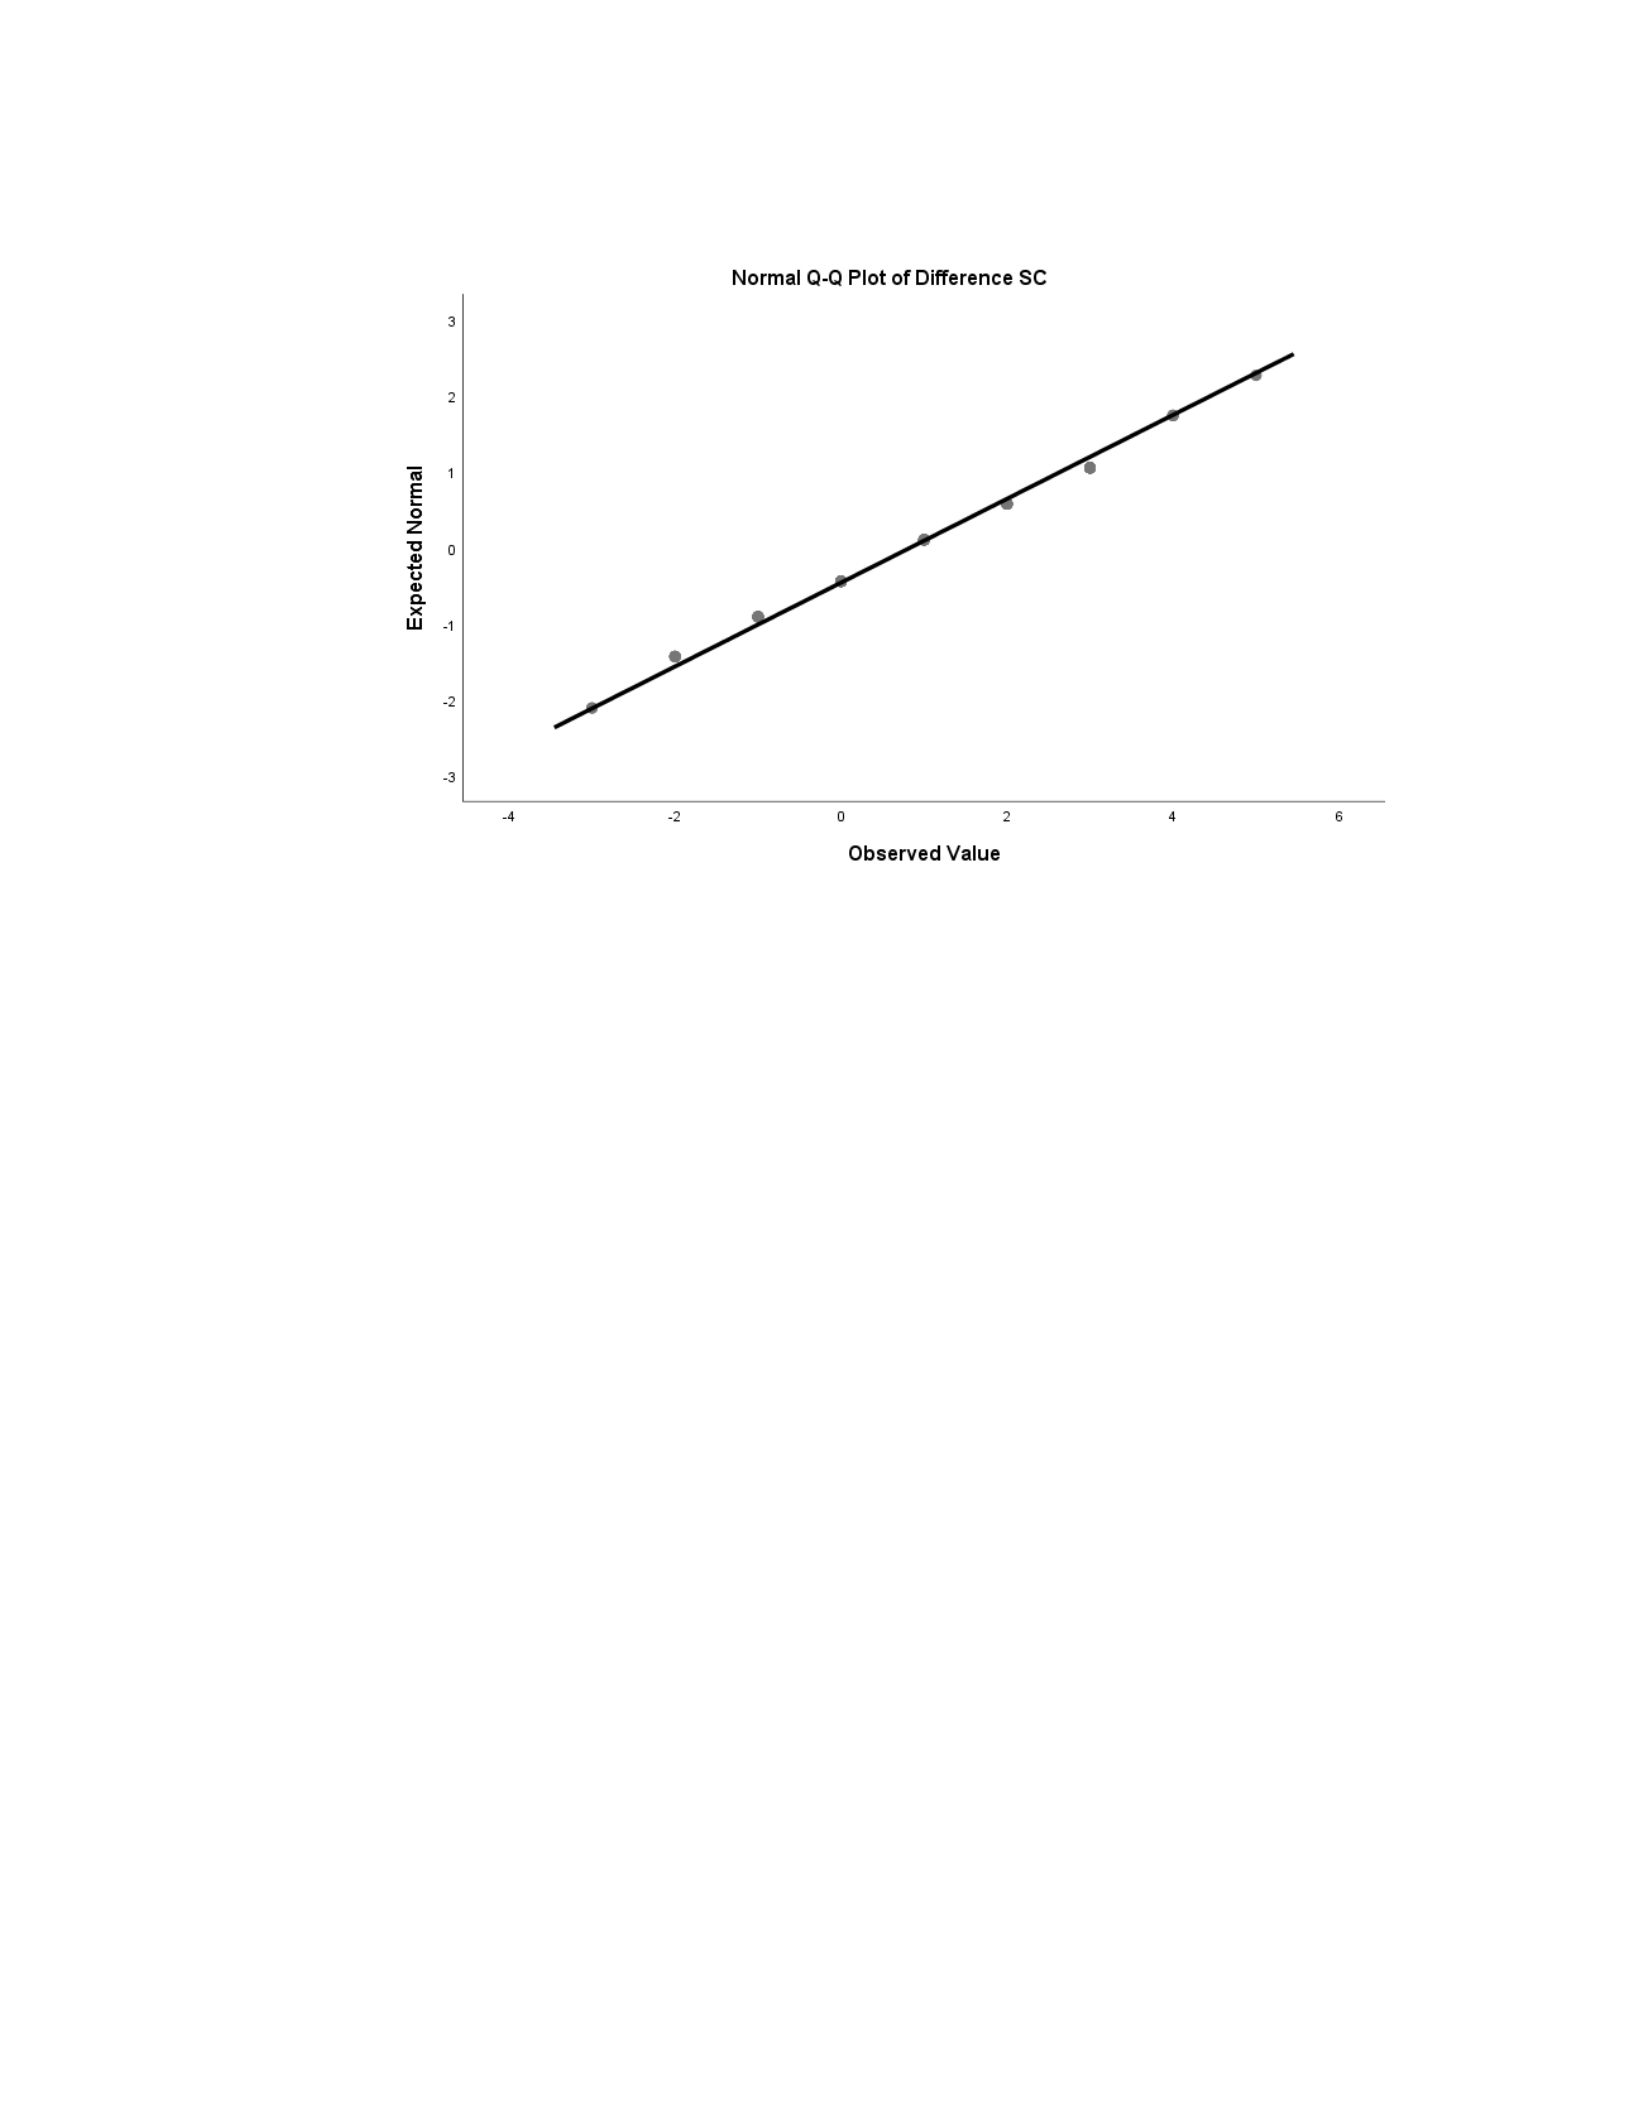
138
Figure 11. Normal Q-Q plot.
Homogeneity of Variance
To ensure that the error variances of the dependent variables of the pre-tests and
post-tests were equal across all levels of the independent variable of the health
information group a Levene’s Test was conducted. The analysis for research question one
yielded p = 037 for the food addiction pre-test and p = .045 for the food addiction post-
test. Both p values were less than .05, therefore, the null hypothesis would be rejected
and homogeneity of variance would not be assumed. The analysis for research question
two yielded p = .062 for symptom count pre-test and p = .058 for the symptom count
post-test. Both p values were greater than .05. Therefore, there would be no rejection of
the null hypothesis in both variables. I also assume to have homogeneity of variance for
both variables. See Table 16.

139
Table 16
Summary of Levene’s Tests for Research Questions 1 & 2
Research Questions
Df1
Df2
Sig.
RQ1 – Pre-Test
1
82
.037
RQ1 – Post- Test
1
82
.045
RQ2 – Pre-Test
1
82
.062
RQ2 – Post-Test
1
82
.058
Note n = 84
Findings Research Question 1
To determine if there were any significant differences in food addiction post-test
scores (while controlling for any differences at pre-test) as measured by the Yale Food
Addiction Scale, among overweight and obese women who receive Social Cognitive
Theory-based health information compared to women who receive non-Social Cognitive
based health information, I used an analysis of covariance. After conducting the analysis,
the results indicated that after controlling for the pre-test there was no significant
differences in food addiction post-test scores of the Social Cognitive Theory-based health
information Group and the non-Social Cognitive based health information group. F(1,
81) = 1.252, p. = .266 n² =.015. Therefore, I would fail to reject the null hypothesis for
the first research question and assume that there is no difference between the groups.
Table 17 provides a summary of the ANCOVA analysis below.

140
Table 17
Results of ANCOVA Analysis
Tests of Between-Subjects Effects
Source
Type III Sum
of Squares
df
M Se
F
Sig.
Partial Eta
2
Corrected Model
76.078
a
2
38.039
10.708
.000
.209
Intercept
27.100
1
27.100
7.629
.007
.086
FAS_UT_PreT
62.316
1
62.316
17.543
.000
.178
Group
4.448
1
4.448
1.252
.266
.015
Error
287.731
81
3.552
Total
1464.000
84
Corrected Total
363.810
83
a. R Squared = .266 (Adjusted R Squared = .248)
The profile plot generated after conducting the ANCOVA analysis shows study
participants in the social cognitive theory group had higher food addiction post-test
scores (M = 4.02, SD = 2.247) when compared to food addiction post-test scores (M =
3.21, SD = 1.868) of the study participants in the non-social cognitive theory group. The
profile plot below displays food addiction post-test mean scores by group (see Figure 12).
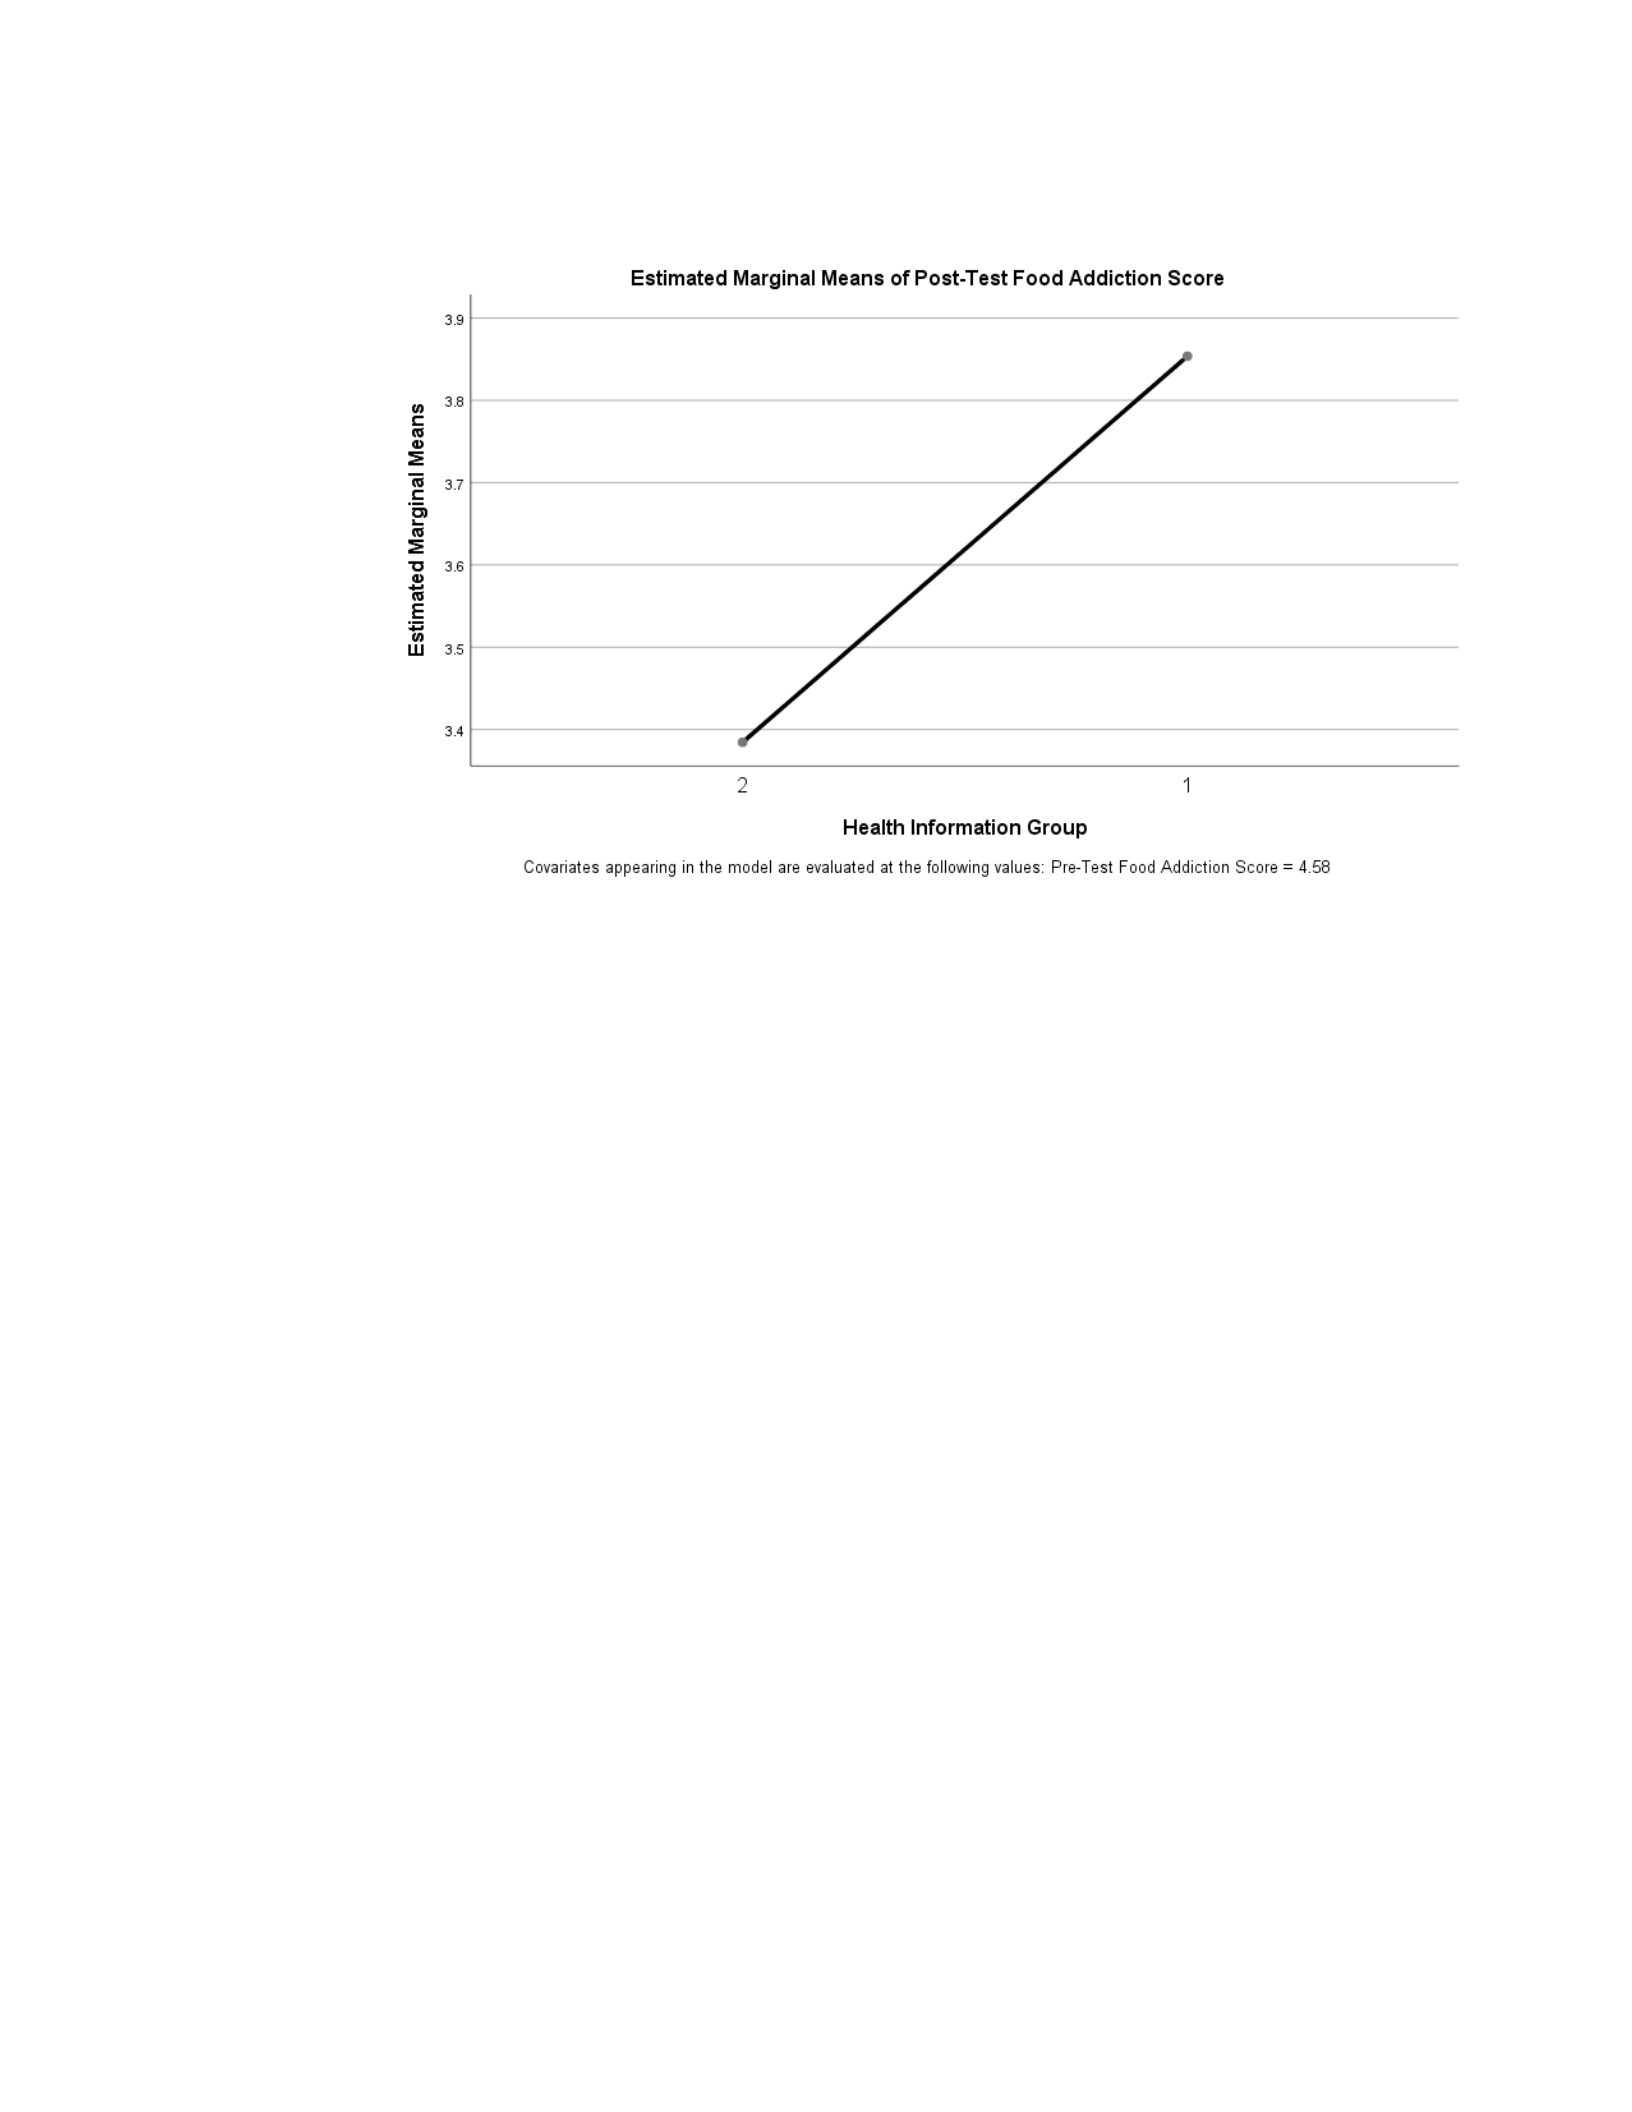
141
Figure 12. Profile plot.
Findings Research Question 2
ANOVA was selected to determine if the Social Cognitive Theory-based health
information had any effect on symptom count post-test scores, as measured by the Yale
Food Addiction Scale, among obese and overweight women when compared to obese and
overweight women that received the non-Social Cognitive based health information. The
independent variable was the Social Cognitive Theory-based health information, and the
dependent variable was the symptom count post-test scores as measured by the Yale
Food Addiction Scale. Table 18 displays the multivariate tests and the main effect of the
health information was not significant, Pillai’s Trace (1) =.171, p = .681 and Wilk’ss (1)
= .171, p = .681 with a large effect-size in Partial ETA2 = 0.002. Table 19 displays the
tests of within-subjects effects ANOVA and displays that the within-subjects main effect
of the health information group measure across two time points for the was not

142
significant, Greenhouse-Geisser, F(1, 82) = 11.859, p = .002. Table 20 displays the
Levene’s test of equality of error variances. The analysis indicates no significant
differences in the pre-test symptom count score (p = .062) and post-test symptom count
scores (p = .058). Therefore, I would fail to reject the null hypothesis and assume
homogeneity of variance. Finally, Table 21 features the tests of between-subjects effects
which provides a summary of the ANOVA analysis. After conducting the analysis, the
results indicated that there were no significant differences in symptom count post-test
scores of the Social Cognitive Theory-based health information Group and the non-Social
Cognitive based health information group. F (1, 82) = 2.838, p. = 0.096, n² = .0033.
Therefore, I would fail to reject the null hypothesis for the second research question.
Table 18
Multivariate Tests
Effect
Value
F
Hypothesis
df
Error
df
Sig.
Partial
Eta
2
Health
Information *
HI_Group
Pillai’s
Trace
.002
.171b
1
82
.681
.002
Wilks’
Lambda
.998
.171 b
1
82
.681
.002
Hotelling’s
Trace
.002
.171 b
1
82
.681
.002
Roy’s
Largest
Root
.002
.171 b
1
82
.681
.002
Design: Intercept + HI_Group Within Subjects Design: Health Information
Exact statistic

143
Table 19
Tests of Within-Subjects Effects
Source
Type
III Sum
of
Squares
df
M S
F
Sig.
Partial
Eta 2
Health
Information
Sphericity
Assumed
30.006
1
30.006
17.550
.000
.176
Greenhouse-
Geisser
30.006
1
30.006
17.550
.000
.176
Huynh-Feldt
30.006
1
30.006
17.550
.000
.176
Lower-
bound
30.006
1
30.006
17.550
.000
.176
Health
Information
*
Sphericity
Assumed
.292
1
.292
.171
.681
.002
Health
Information
Group
Greenhouse-
Geisser
.292
1.000
.292
.171
.681
.002
Huynh-Feldt
.292
1.000
.292
.171
.681
.002
Lower-
bound
.292
1.000
.292
.171
.681
.002
144
Table 20
Levene’s Test of Equality of Error Variances
Levene
Statistic
Df1
Df2
Sig
Pre-Test
Symptom
Count Score
Based on
Mean
3.575
1
82
.062
Post-Test
Symptom
Count Score
Based on
Mean
3.704
1
82
.058
Table 21
Summary of ANOVA Analysis for Research Question 2
Source
Type III
Sum of
Squares
df
M S
F
Sig.
Partial
Eta 2
Intercept
2295.482
1
2295.482
591.895
.000
0.878
Group
11.006
1
11.006
2.838
0.096
0.033
Error
318.012
82
3.878
MS = Mean Square
Sig. Significance
The profile plot generated after conducting the ANOVA analysis shows that study
participants in the social cognitive theory group had higher food symptom pre-test scores
(M = 4.313, SD = 1.776) and post-test scores (M = 3.57, SD = 1.889) when compared to
food symptom pre-test scores (M = 3.90, SD = 1.411) and post-test scores (M = 2.98, SD
= 1.569) of the study participants in the non-social cognitive theory group. The profile
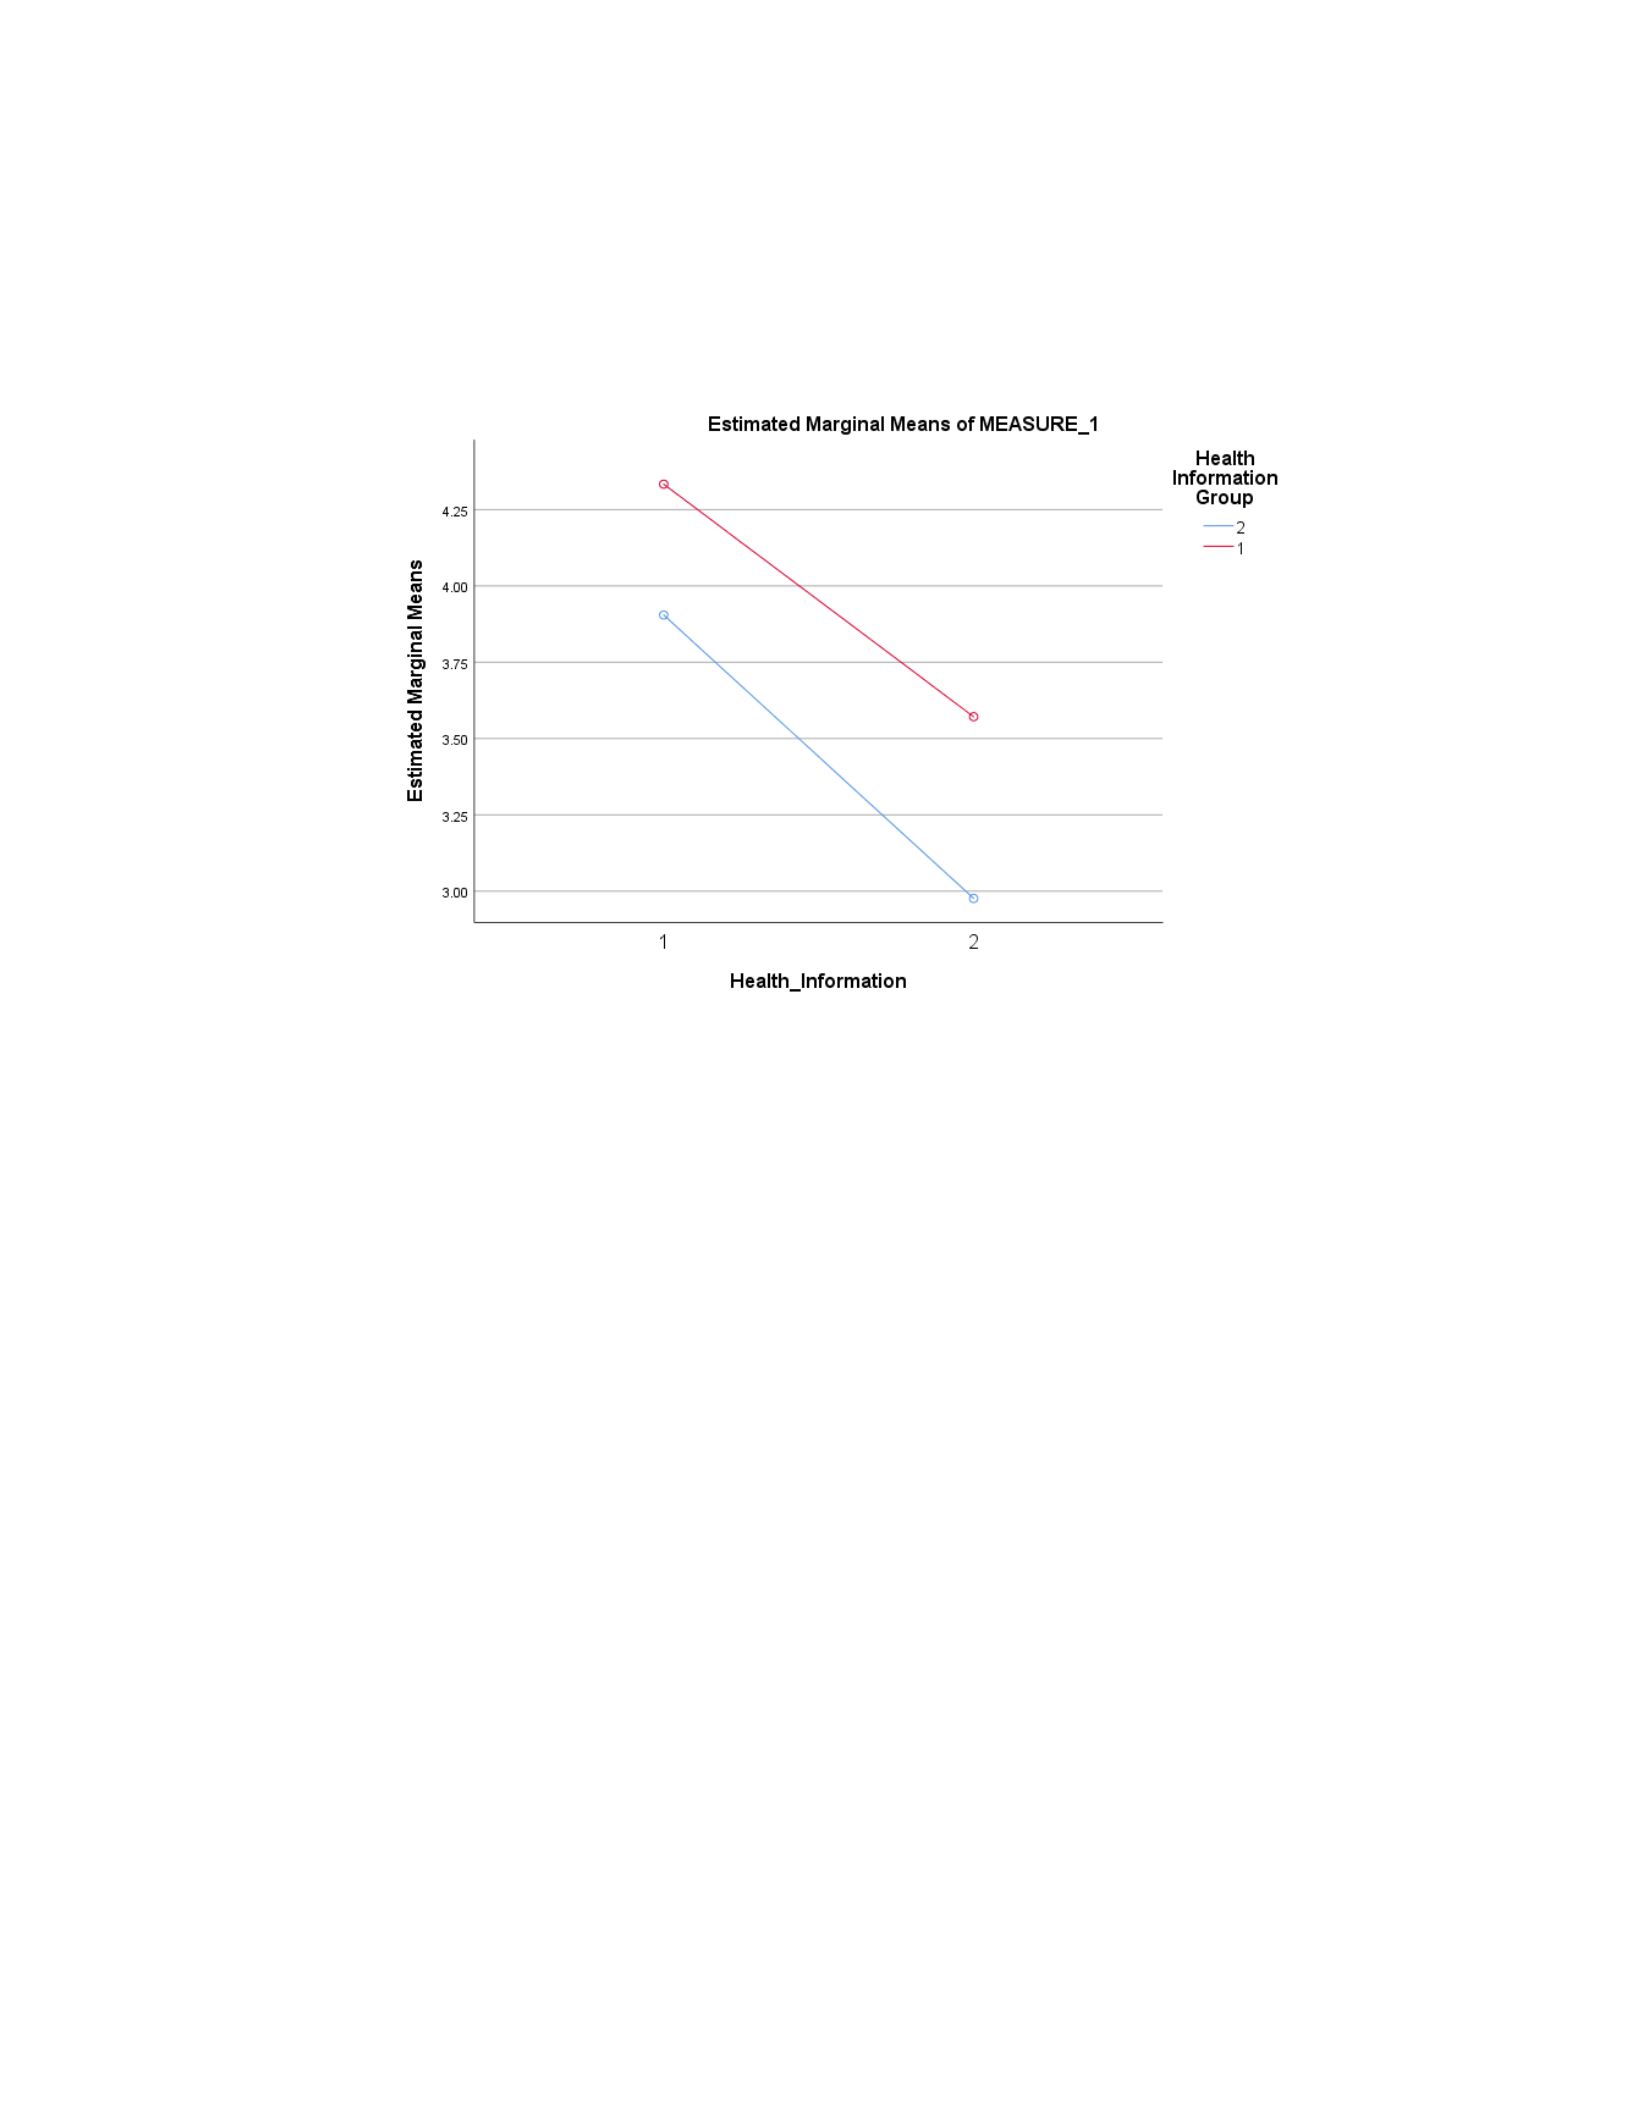
145
plot below displays food symptom pre-test and post-test mean scores by group (see
Figure 13).
Figure 13. Profile plot.
Additional Statistical Tests: Paired-Samples T Test, Change Score Analysis, and
ANCOVA
Due to the ANCOVA and ANOVA analysis yielding results that were not
statistically significant, three additional statistical tests of the hypothesis were conducted.
The first statistical test that was conducted was a Paired-Samples T Test Analysis.
However, prior to conducting this analysis, a preliminary analysis was performed to
verify no violation of the assumption of normality. Table 22 displays descriptives for the
paired t-test which features the difference in the symptom count score, Skewness = -.052,
Kurtosis = -4.96. Table 23 displays normality for the paired t-test of the symptom count
score difference, Kolmogorov-Smirnov p = .000, Shapiro-Wilk p = .013. Both scores are
146
statistically significant, therefore, there is a need to reject the null hypothesis and note
that the data is not normally distributed. A paired sample t-test depicts paired samples
correlation and is displayed in Table 24. These results are favorable. The analysis found
statistical significance (p=≤.001) and a strong correlation (r = .403, n = 84).
Table 22
Descriptives for Paired T-Test
M
SD
Skewness
Kurtosis
Symptom Count Score (Differences)
.85
1.840
-.052
-.4.96
Table 23
Normality for Paired T-Test
Kolmogorov-
Smirnov
Shapiro-
Wilk
Statistic
Sig.
Statistic
Sig.
Symptom Count Score (Differences)
.145
.000
.962
.013
Table 24
Paired Sample T-Test - Paired Samples Correlations
N
Correlation
Sig.
Pre-Test &
Post Test
Symptom
Count Scores
84
.403
.000
The second statistical test that was conducted was an ANOVA Change Analysis.
This test was used to measure the difference in the symptom count post-test scores
between groups. The results were favorable as well, the Levene’s Test which found
147
statistical significance (p = 0.018). Therefore, I would reject the null hypothesis and
assume that the error variance of the dependent variable is not equal across groups and
homogeneity has not been achieved. An ANOVA analysis conducted on the difference
between the social cognitive theory-based health information group and the non- social
cognitive theory-based health information group was found to not be statistically
significant F (1, 82) = .171, p. = 0.681, n² = 0.171 (Table 25). Normal Q-Q Plot displays
the symptom count difference in Figure 14.
Table 25
Results of ANOVA Analysis of Symptom Count Score Difference
Tests of Between-Subjects
Effects
Source
Type III Sum
of Squares
df
M S
F
Sig.
Partial
Eta
2
Corrected
Model
.583a
1
.583
.171
.681
.171
Intercept
60.0124
1
60.012
17.550
.000
17.550
HI Group
.583
1
.583
.171
.681
.171
Error
280.405
82
3.420
Total
341.000
84
Corrected Total
280.988
83
a. R Squared = .002 (Adjusted R Squared = .010)
a. Computed using alpha = .05
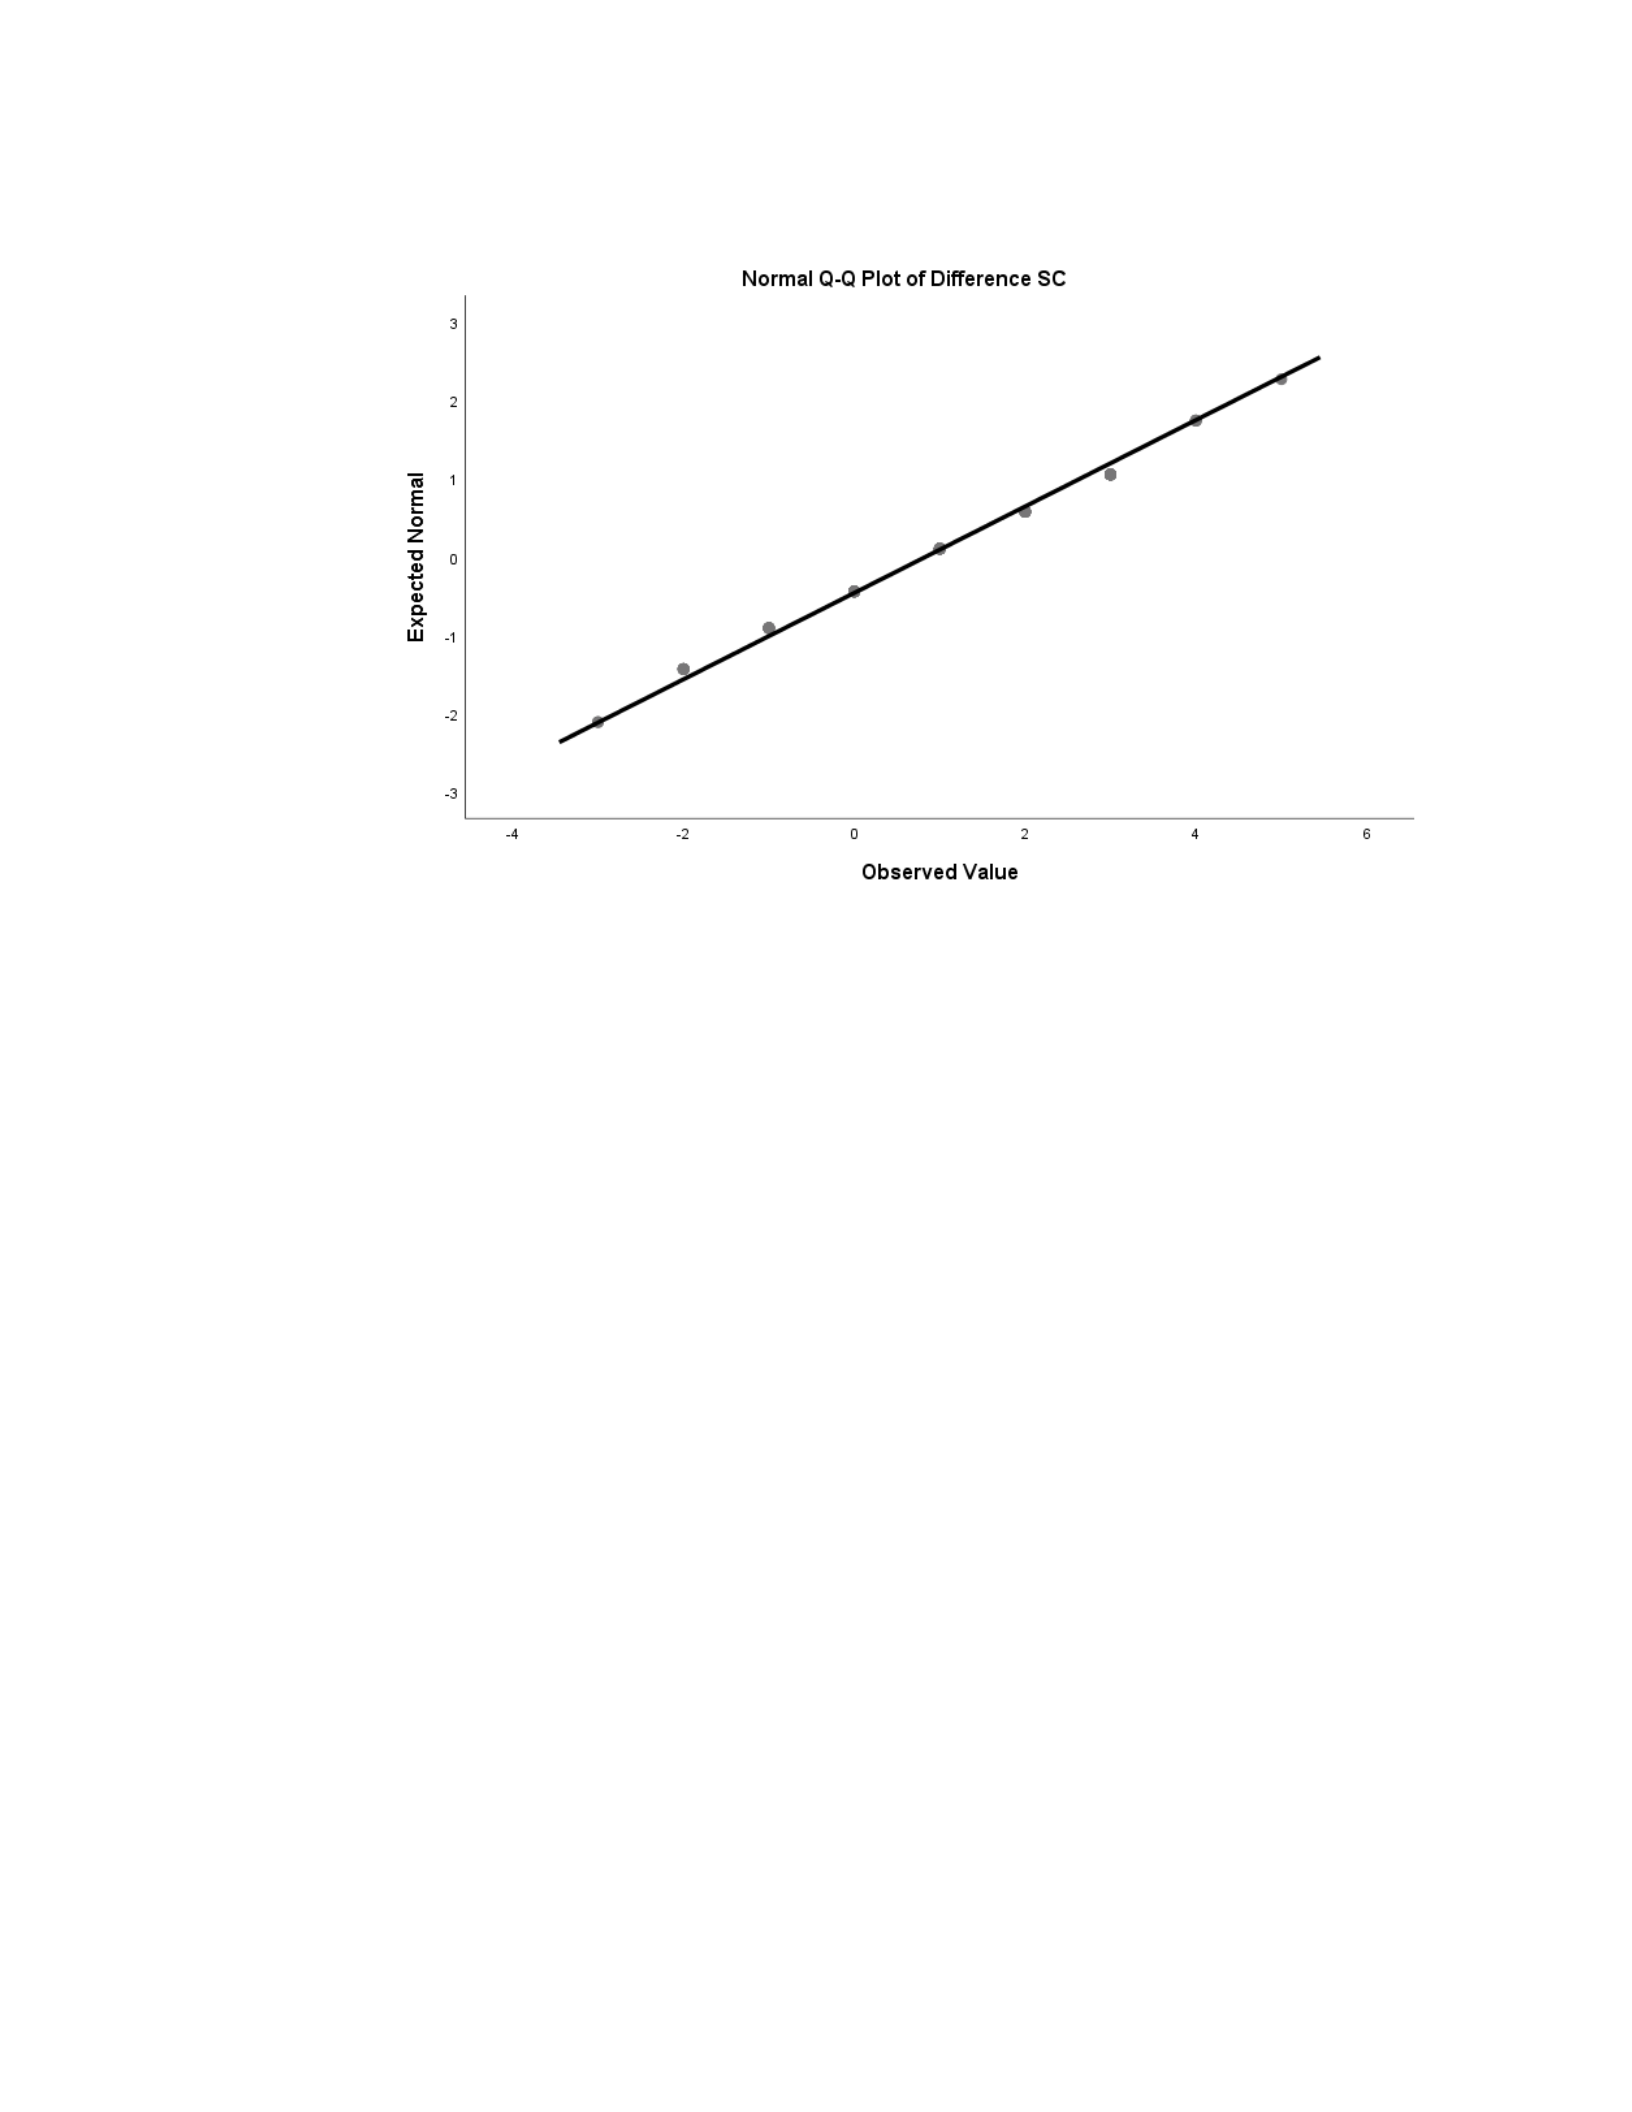
148
Figure 14. Normal Q-Q plot.
Even though I used a convenience sample and utilized non-random sampling to
secure my participants, the data collected from my study participants was obtained from a
wide range of study participants to reduce the chances of my study having lower validity
and to increase the generalizability of my data. Frankfort-Nachmias & Nachmias (2008)
stated that it is important to consider and compensate for nonrandom samples because
they have lower validity than random samples. Increased generalizability increases a
study’s external validity and therefore offsets the threat to validity that a non-random
sampling approach can invite. My study participants were located nationwide and from
various ethnic backgrounds, so my data and findings can be generalized to the intended
target of the study.
The third statistical test that was conducted was an ANCOVA analysis on the
food addiction symptom count scores. The original approach to analyzing food addiction

149
symptom count scores was an ANOVA analysis. As previously mentioned, I chose to
conduct an ANOVA analysis on the food addiction symptom count scores because I
wished to examine the changes between the pre-test and post-test to understand the
differences between the means of the independent variable. However, in order to ensure
the data has received as thorough an analysis as possible, an ANCOVA was conducted as
well. Conducting the ANCOVA on the food addiction symptom count scores would
allow me to control for the pre-test score while determining if any differences existed in
study participant food addiction symptom count scores. Table 26 and Figure 15 displays a
brief summary below. The results of the ANCOVA analysis indicated no statistically
significant difference between the group health information and the post test symptom
count scores, F(1, 82) = 1.369, p = .24. Therefore, I accept the null hypothesis.

150
Table 26
Results of ANCOVA Analysis of Symptom Count Scores
Tests of Between-Subjects Effects
Source
Type III Sum
of Squares
df
M S
F
Sig.
Partial Eta
2
Corrected
Model
44.909
a
2 22.454 8.670 .000 .176
Intercept 25.614 1 25.614 9.889 .002 .109
PT Symp.
Count
37.468 1 37.468 14.466 .000 .152
Group
3.545
1
3.545
1.369
.245
.017
Error
209.793
81
2.590
Total 1155.000 84
Corrected Total
254.702
83
a. R Squared = .176 (Adjusted R Squared = .156)
b. M S = Mean Squared
c. PT Symp. Count = Post Test Symptom Count Score
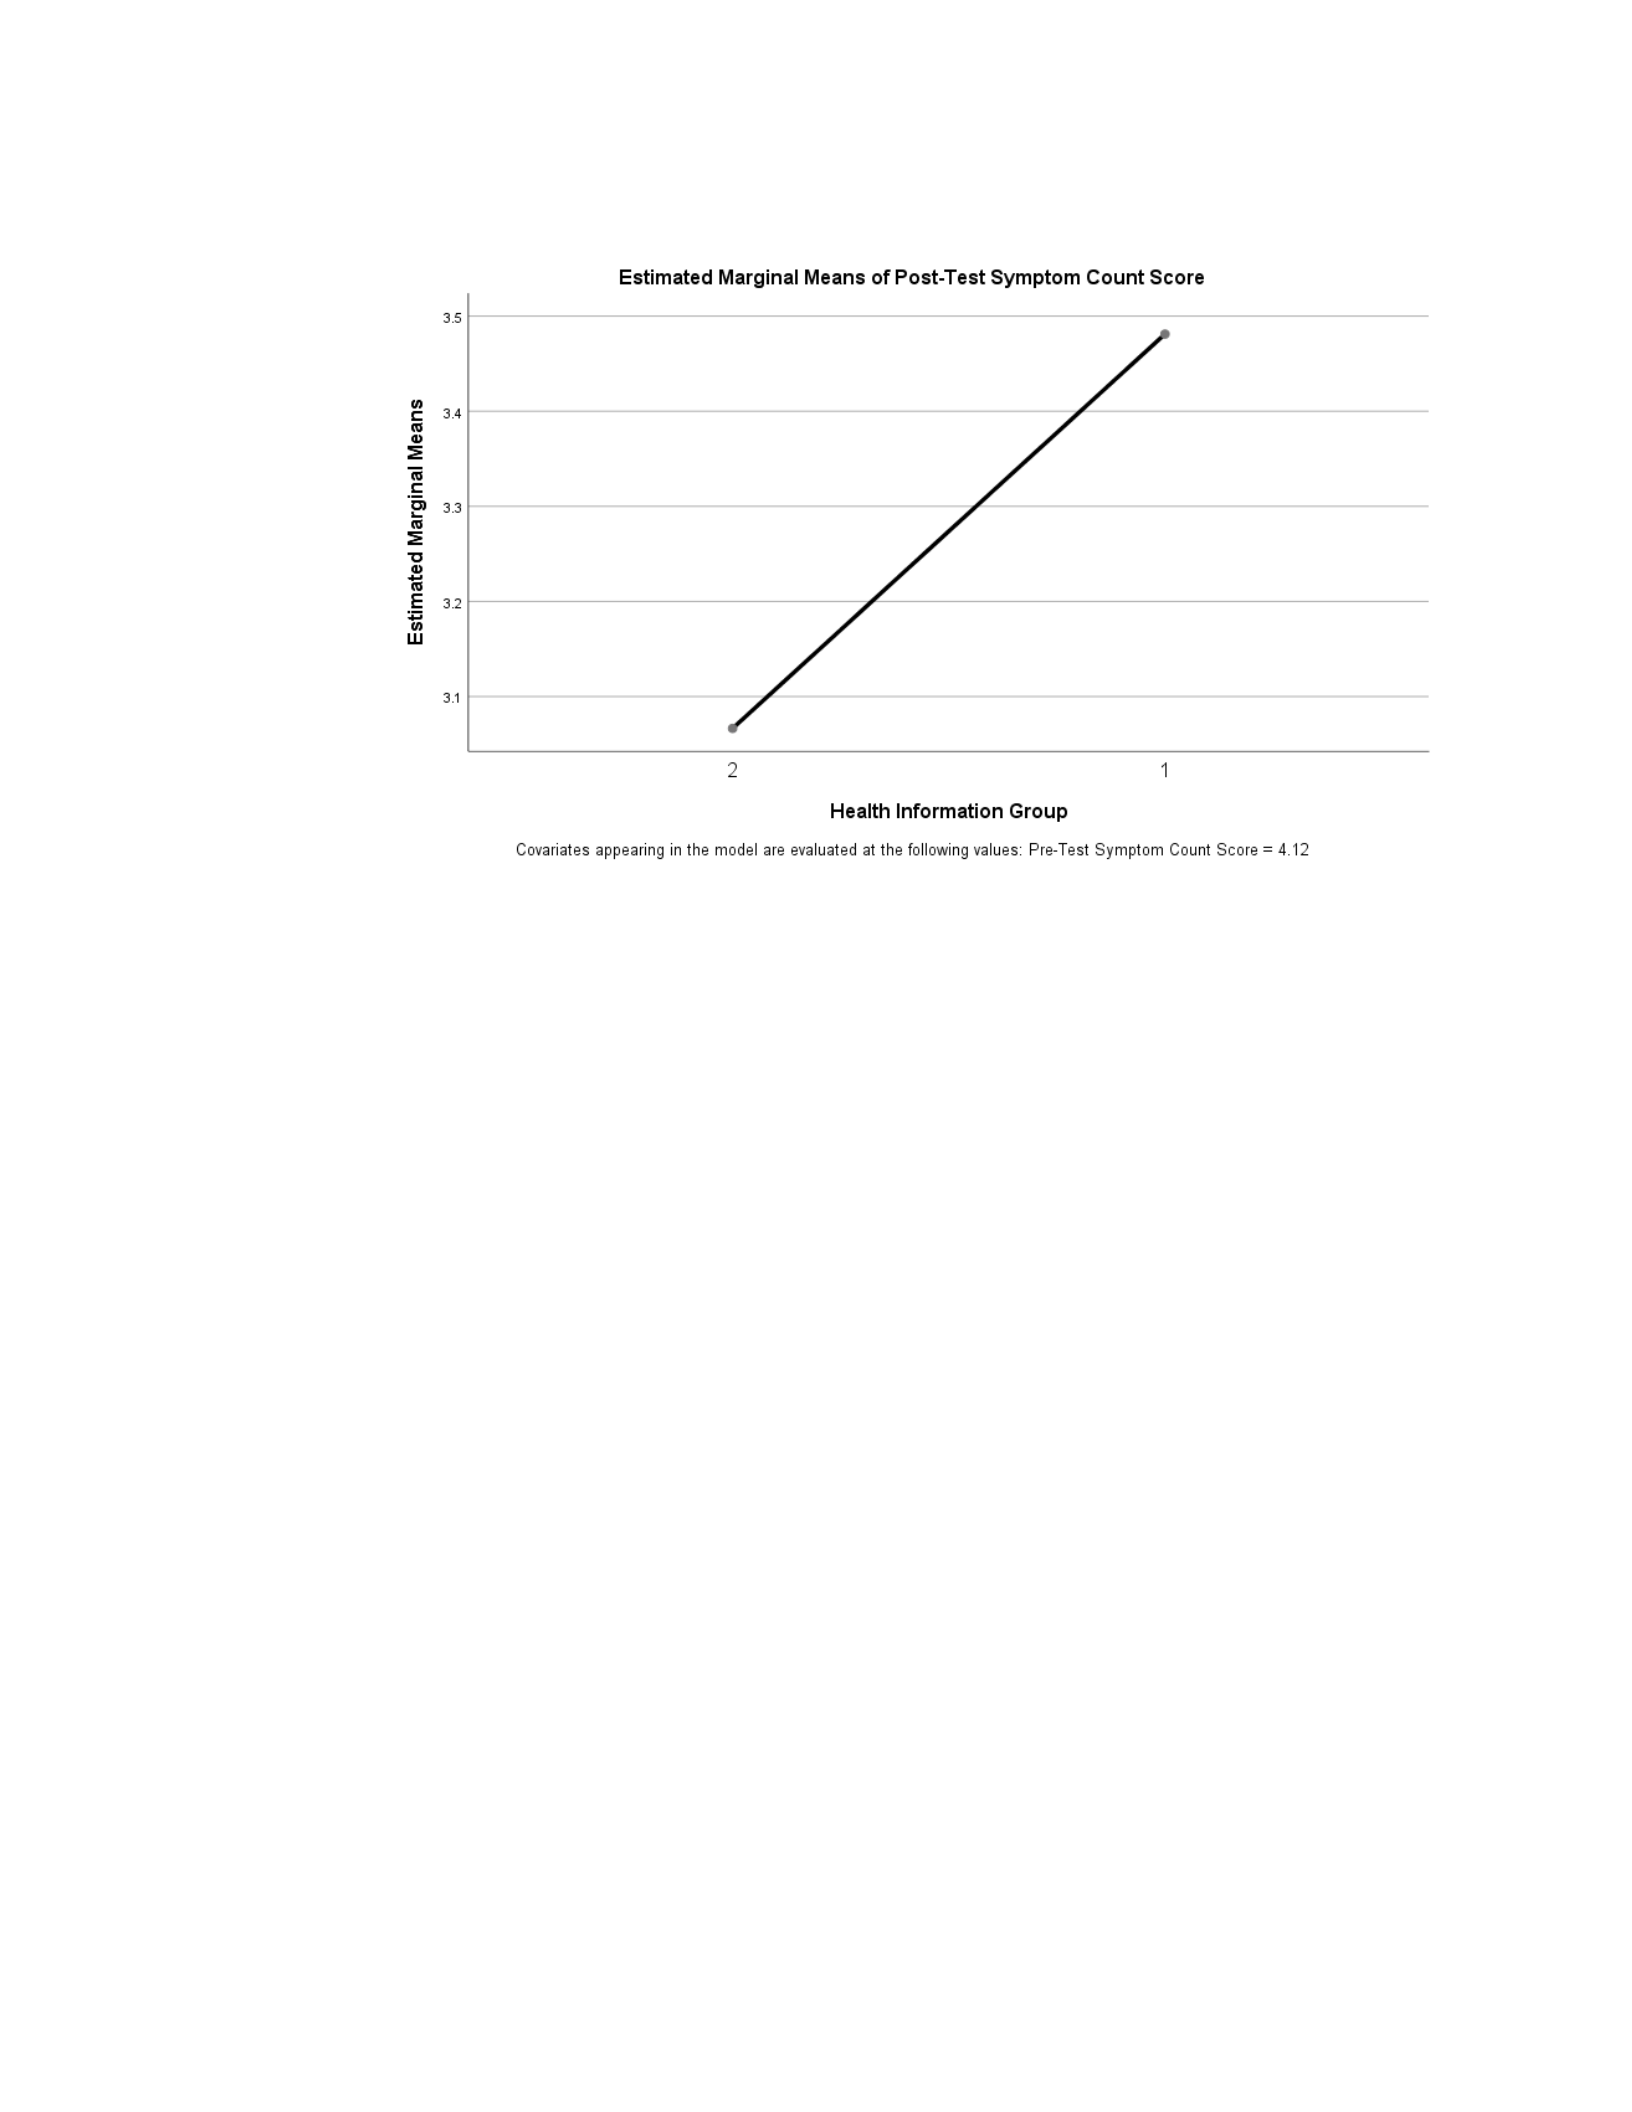
151
Figure 15. Estimated marginal means.
Summary
The struggle of obesity and being overweight continues to afflict almost 70% of
Americans (Fortuna, 2012). Emerging research has found that potential food additives
such as MSG and HFCS may be contributing to the obesity epidemic (Insawang et al.,
2012; Lowndes et al., 2012). This obesity epidemic is due to the consumption of MSG
and HFCS linked to food addiction, food addiction symptoms such as overeating, food
cravings, and the brain’s addictive response to food Blaylock (1999).
This study utilized key facets of social cognitive theory to create health
information that would increase the knowledge of awareness of foods and food additives
that lead to food addiction and food addiction symptoms. This new awareness would
stand as a catalyst and as a precondition for change to study participant’s health
behaviors. There is a gap in the literature regarding the effectiveness of presenting health

152
information to reduce intake of food additives linked to food addiction and obesity. I
hope that this study will contribute to future research in this area.
Eighty-four overweight and obese women were recruited to examine the
effectiveness of using social cognitive theory -based health information with obese and
overweight women to the effectiveness of using social cognitive theory-based health
information to reduce or eliminate food addiction and food addiction symptoms. I
examined the research questions and based on analysis findings, and I accepted or
rejected the research questions.
After conducting an ANCOVA analysis which entailed comparing the food
addiction scores of the social cognitive theory-based health information group and food
addiction scores of the non- social cognitive theory -based health information group
while controlling for the pre-test scores, I found that the results were not statistically
significant (p = 0.096). The ANOVA analysis found that the results were not statistically
significant (p= 0.266). Due to these results I conducted a Pre-test Post-test Analysis and
found statistical significance (p = ≤.001) and a strong correlation (r = .403, n = 84).
In chapter 5, I will describe my interpretation of the data and information gathered
for the study and report the social implications. Finally, I will discuss my study
limitations and potential areas of further exploration and research. I will end the chapter
with a summary of the study.

153
Chapter 5: Discussion, Conclusions, and Recommendations
The purpose of this quantitative, quasi-experimental study was to compare the
effects of health information based on social cognitive theory and health information not
based on social cognitive theory on food addiction among obese and overweight women.
Eighty-four obese and overweight women were recruited from a private school in
Chicago, IL., Walden University online participant pool, Findparticipants.com, and
Researchandme.com for this study. The Yale Food Addiction Scale was used to measure
changes in food addiction and food addiction symptoms after providing health
information based on social cognitive theory and health information not based on social
cognitive theory to both groups.
This study was conducted for four reasons. First, this study was conducted
because over 60% of Americans are obese and overweight (Fortuna, 2012). People who
are overweight and obese feel the pangs of expanding waistlines and the powerlessness to
stop the eating behaviors that contribute to their negative feelings. The second reason this
study was conducted is that few researchers have explored managing food addiction
symptoms (cravings, overeating, guilt, and anxiety) with social cognitive theory to
improve food choices. I have witnessed these struggles among close family members in
various situations. For example, I have witnessed the look of sadness in my mother’s face
when she could not secure quality health care at doctor’s offices. In those situations,
doctors recommended that she merely exercise greater control and willpower over her
food choices as the cure to any health problem. Sadly, my mother passed away due to

154
obesity-related complications in October 2016. Although these events were sad, they
propelled me to dedicate my life to researching and understanding obesity.
The third reason this study was conducted is that researchers had uncovered
significant findings related to this study. For example, obesity and being overweight are
not simply matters of exercising willpower and self-control. Certain foods that are high in
fat, salt, and sugar activate the brain’s reward system and have an addictive effect (Göbel,
Tronnier, & Münte, 2017). Those who suffer from obesity and overweight experience
physiological changes similar to the changes drug addicts experience (Barry et al., 2009;
Wilson, 2010). Research has shown social cognitive theory to be effective in addressing
addictive behaviors such as drug addiction, alcohol addiction, and smoking cessation
(Bricker et al., 2010). The final reason for this study is that there was a gap in the
literature regarding the effectiveness of presenting psychologically based health
information (such as the components of social cognitive theory) to reduce the intake of
food additives that have been linked to food addiction and obesity.
Interpretation of the Findings
My findings confirmed and extended knowledge in the discipline. The findings
were compared with what has been found in the peer-reviewed literature. The Yale Food
Addiction Scale was used to measure 84 overweight and obese female participants for
food addiction and food addiction symptoms in a quasi-experimental study. I divided the
participants into two groups, one group who received health information based on social
cognitive theory and the other group who received health information not based on social

155
cognitive theory, for 4 weeks. Once the data were collected, I conducted an ANCOVA
and an ANOVA to answer the research questions.
Research Question 1
The results of the ANCOVA analysis indicated no significant difference in the
posttest food addiction scores for Group 1 and Group 2, controlling for the pretest.
Therefore, it was necessary to fail to reject the null hypothesis and accept the alternative
hypothesis. In addition, the mean food addiction scores for Group 1 decreased.
Although these results were not statistically significant, the food addiction
posttest scores decreased for both groups. This supports one component of Bandera’s
(2004) theory, which states that having knowledge of a health benefit creates a
precondition for change. The precondition for change was initiated when participants
were exposed to the health information. It is also possible that I unwittingly, by
discussing the effects of foods that contained MSG and HFCS with both groups, initiated
a precondition for change in Group 2 participants. Bandura (1997, 2004) stated that one
of the aspects of a precondition for change is that a person becomes more aware of the
consequences of his or her health behavior. This finding was noted in a recent food
addiction study by Schulte et al. (2019). Although the participants who were classified as
food addicted were expected to consume more highly processed foods than the control
group, they consumed the same amount as the control group (Schulte et al., 2019).
Schulte et al. speculated that the reason for this eating behavior was that food addicted
participants became more aware of their eating behaviors and therefore cut down or

156
abstained from consuming highly processed foods that have been linked to food
addiction.
There is another possible reason for the result. Schulte et al. (2019) delved deeper
into food addiction by studying the amount of highly processed foods consumed and
monitored (a) craving, (b) enjoyment, (c) intention to consume in the future, and (d)
likelihood to consume the food if offered for free. Schulte et al. assumed that food
addicted participants would consume more highly processed foods than their normal
weight participants. Instead, Schulte et al. found no difference in the number of calories
consumed that consisted of highly processed foods or minimally processed foods
compared to their normal weight counterparts. Schulte et al. speculated that food addicted
participants consumed highly processed foods in a less intentional manner and more
compulsive manner compared to those without food addiction. Because of the health
information provided in the current study, participants consumed highly processed food
in a more intentional manner and a less compulsive manner due to receiving either
theory-based health information or non-theory-based health information that identified
highly processed foods as containing HFCS and MSG. This was reflected in two ways.
First, the overall posttest mean food addiction scores decreased for both groups (M =
3.62, SD = 2.094) compared to the pretest scores (M = 4.58, SD = 1.915). Second, the
study participants experienced a decrease in their BMIs, which demonstrated that
participants experienced weight loss.
Finally, a recent study just (Ouellette et al., 2018) on food addiction may shed
more light on the Yale Food Addiction Scale and food addiction. Ouellette et al. (2018)

157
observed that those who suffer from food addiction symptoms do not always select the
questions that compose the clinical impairment section of the Yale Food Addiction Scale.
Ouellette et al. found that people who suffer from food addiction symptoms can be food
addicted without indicating that they experience clinical impairment. Ouellette et al. also
found that a better indicator of food addiction is withdrawal symptoms and hedonic
hunger. Ouellette et al. suggested removing the clinical distress and impairment criteria
for food addiction and using symptom count scores instead. According to Ouellette et al.,
participants who scored a symptom count of 3 and above should be considered as having
met the clinical criteria for food addiction. When Ouellette et al. implemented this
approach, the number of participants increased from 16% to 35% of the total sample
meeting the criteria for food addiction.
Research Question 2
The second research question was analyzed with an ANOVA analysis. The results
of the ANOVA analysis indicated that there was no significant difference in the symptom
count scores of the social cognitive theory-based health information group and the non-
social cognitive theory-based health information group. Therefore, I would reject the null
hypothesis and accept the alternative hypothesis. However, the mean symptom count
scores decreased for both groups.
These findings extend knowledge in the discipline and Bandura’s social cognitive
theory even though there was a lack of statistically significant results which indicates that
health information had little impact on symptom count scores. However, the decrease to
study participant BMIs shows potential for the health information especially because

158
these changes took place over the course of the four-week study. This is because a
decrease to study participant’s BMIs indicates that study participants changed their eating
behaviors and subsequently lost weight.
The social cognitive theory-based health information presented to the social
cognitive theory group followed Bandura’s recommendation for maximum effectiveness.
Bandura (1986) suggested that health information should “instill in people the belief that
they have the capability to alter their health habits and emphasize that success requires
perseverant effort so that people’s sense of personal efficacy is not undermined by a few
setbacks” (p. 439). In addition to sharing with study participants how to avoid foods
containing the food additives MSG and HFCS so that study participants can reduce or
eliminate food addition and symptoms of food addiction, the health information for the
social cognitive theory-based group emphasized the importance of seeing themselves as
being capable of altering their health habits.
Although the result was not statistically significant, the decrease in mean
symptom count also confirms Roach et al. (2003) finding discussed in chapter two that
utilizing even one component of social cognitive theory (self-efficacy) in sharing health
information resulted in improvements to study participant’s eating behavior. Evidence of
improvements in study participants’ eating behavior was seen in the decrease in the mean
symptom count and that almost 60% of the study participants experienced a decrease in
symptom count scores.

159
Knowledge Quizzes
The first set of study participants from both groups that completed the four-week
study were reminded once a week for five weeks to complete the knowledge quiz without
success. At first, no study participants would take the knowledge quizzes. Once I
increased the frequency of reminders from once a week to every other day (three times a
week) and changed how the reminder was written, study participants from both groups
began to complete the knowledge quiz. Study participants responded better to three
things 1) more reminders and 2) reminders that were conversational and informal in tone
3) and emphasizing that study participants cannot pass or fail the quiz.
Changes to BMI
It was important to collect study participants height and weight information to
calculate BMI scores and to determine eligibility for this study. The minimum BMI score
to be eligible for the study was 25 kg/m. A BMI score of 25 kg/m – 29 kg/m indicated
that a study participant was overweight and a BMI score greater than 30 kg/m indicated
that the study participant was obese (King, 2013). BMI scores are calculated using a
person’s height and weight. A BMI score can change only if a person’s weight changes.
Decreases to a BMI score means that a person lost weight and increases to a BMI score
means that a person gained weight. Whereas, no changes to a person’s weight means that
a person’s weight didn’t change.
I expected that study participants that received the social cognitive theory-based
health information, relative to those without, would have greater decreases to their BMI
scores, due to decreased food addiction symptoms. The decrease in food addiction

160
symptoms would in turn decrease or eliminate consumption of foods containing MSG
and HFCS which would result in weight loss. Instead, 40.5% of participants that received
the social cognitive theory-based health information experienced a decrease in BMI
scores versus 61.9% of participants without social cognitive theory-based health
information. Although an analysis of the food addiction symptom scores yielded results
that were not statistically significant, the Levene’s test did indicate high correlation. This
is not to dispute the lack of statistical significance; statistical significance is important.
Nevertheless, the fact that study participants, in four weeks, experienced a positive
change to their BMI scores is noteworthy.
Limitations of the Study
Four limitations arose from the execution of this study. The first limitation -
attrition impacted post-test completion. Prior to beginning this study, I anticipated and
estimated a 20% post-test completion average. One hundred and seventy-three study
participants completed the pre-test. However, as the study progressed and study
participants completed the four-week study, a pattern began to emerge and I noticed that
post-test completion averaged around 50%. Further research into attrition rates yielded
two insightful findings. First, according to Lee (2003), panel studies similar to this study
suffer from a high degree of attrition between surveys due to non-response. Second, Zhou
and Fishbach (2016) also noted that the average attrition rate for a typical web
experiment (this study meets the criteria for a web experiment due to recruiting,
surveying, and distributing information online) is 34%, however depending on the

161
dynamics of the web experiment, attrition rates can reach 87%. A lab-based study, by
comparison, experiences 0% attrition in 96% of lab studies (Zhou and Fishbach, 2016).
The attrition rate for this study was 52%. One hundred and seventy-three study
participants completed the pre-test and 84 study participants completed the post-test.
Lack of post-test completion was an unanticipated challenge and resulted in additional
time, and financial resources spent recruiting additional study participants to increase the
sample size. Two factors could have played a role in 52% attrition rate. The first factor is
time. Although study participants were aware that the study was four weeks in duration,
and the importance and requirement of completing the post-test, perhaps study
participants were only content to receive the health information and had no interest in
completing the post-test. The second factor is the nature of the study being conducted
online as opposed to face-to-face. Reips (2002) findings also echo this sentiment by
stating that study participants have a low commitment level to online studies due to the
lack of physical interaction.
The second limitation was study participant comfort level with working with
technology. When given the opportunity to provide feedback via the last question in the
post-test, most participants indicated their satisfaction with the study. However, there
were a small number of participants that contacted me after receiving health information
for four weeks and shared with me that they were unable to open the health information.
This challenge was not due to education level. After reviewing the data, and matching the
study participant to their respective education level I discovered that the study
participants possessed at least some level of college education. After confirming that they

162
could not open the link to the narrated slides nor the PowerPoint presentation a PDF
version of the health information was sent.
Third limitation was lack of a control group. Although the results were not
statistically significant, there was an improvement in mean food addiction scores and
mean food addiction symptom count scores. A control group could have been waitlisted.
Waters, George, Chey, and Bauman (2012) conducted a study where the waitlisted
control group was surveyed before and after the study, but received no information
during the study. The waitlisted control group study participants were informed that they
would receive information after the study ended. The opportunity to compare the social
cognitive theory group to the waitlisted control group could have yielded statistically
significant results.
Finally, although there are very researchers that have conducted online studies,
Reips (2002) recommends compensating study participants to prevent attrition. This
study did not offer compensation to study participants because I would need to personally
compensate the study participants. However, it is important to acknowledge that by
offering financial compensation to study participants to complete the post-test it is
possible that attrition rates would have been lower.
Recommendations
This study shows great potential in several areas. First, the study shows great
potential in food addiction research and applying psychological theory to bringing about
a positive change in eating behavior. Although no significant results were found with the
ANOVA and the ANCOVA analysis, the Paired-Samples T-Test analysis yielded

163
favorable results and study participants experienced a decrease in food addiction
symptoms. This favorable outcome demonstrates this study’s second area of great
potential and unveils another option and approach to applying the constructs of social
cognitive theory towards treating food addiction and the symptoms of food addiction for
a sustained amount of time. Third, this study broadens and expands the possibilities of the
frontier of research due to this study being conducted entirely online. Fourth, there is also
the potential for additional discoveries if this study were to be implemented on a broader
scale by future researchers and medical professionals.
If this study were to be repeated, I would recommend the following four items.
First, I would recommend future researchers understand that conducting an online study
can be daunting to the uninitiated. Recruiting online for research studies has been
transformed by the accessibility and convenience of the internet. However, there is a
trade-off for this ease and convenience – lower conversion rates.
Initially, it would appear that neophyte researchers that are just embarking upon
this journey need to only identify the number of study participants that will be needed.
Next, find a website that provides access to a participant pool, conduct the study, analyze
and write up the results and then the neophyte researcher is done. However, a researcher
that endeavors to conduct a study online from start to finish is really initializing a “crash
course” in social media marketing. This crash course will minimally include learning
about online conversion rates, retention rates, digital copywriting, market research
participant pool privacy laws, and automated e-mail marketing campaigns. In addition, a
researcher will have to allocate adequate financial resources and time to account and

164
compensate for conversion rates while recruiting study participants. For example, while
recruiting for this study, I needed 30 additional study participants. Researchandme.com,
sent out my recruiting advertisement to 8,000 potential study participants. Initially, it
appeared that I would have more than enough participants. However, these 8,000
potential study participants converted into 200 people that expressed an interest in my
study and were qualified to participate. I selected 101 people out of the 200 people. Out
of 101 people, only 75 completed the pre-test. Therefore, out of 8,000 potential study
participants, I only had 1% (n = 75) reach “the moment of truth” to enroll in the study.
This pattern was observed with all recruiting sources, even though Researchandme.com
had the best overall conversion rate compared to other recruiting sources.
Second, it is important to understand the privacy rules of websites that allow
researchers to pay to access their pool of research participants. One of the most
challenging items for a researcher is recruiting participants for a study. For a fee, a
researcher can pay to access a panel of people (called a research panel or research pool)
to participate in their research study. However, some websites offering this service have
privacy policies in place to protect their participants. These privacy policies often include
prohibiting a researcher from collecting identifying information such as an e-mail
address, phone number, or a participant’s name. For this study, it was imperative to
secure the name and e-mail addresses of the study participants because I needed to send a
pre-test and a post-test to the same set of participants to measure the effects of the social
cognitive theory-based health information on food addiction scores and symptom count
scores. A majority of market research pool companies label transactions of this type as

165
bi-directional communication and this type of communication is a violation of their
privacy policy.
Third, since conducting an ANOVA and ANCOVA requires comparing responses
over the duration of a study, future researchers should be prepared to compensate for
study participant retention and lack of post-test completion by recruiting a larger sample
size. Although, 52% of study participants that completed the pre-test completed the post-
test, I assumed that at least 80% of people that initiated the study would want to finish the
study and complete the post-test and knowledge quizzes. However, I had to send
numerous reminder e-mails during the week in order to urge study participants to
complete the post-test. Eventually, 84 participants completed the post-test, but the
completion was reached quite slowly over the course of several months.
Finally, the percentage of those that were food addicted was lower than expected
Although food addiction research is a relatively new and emerging field, prior research
suggests that those that are overweight and obese would have a higher rate of food
addiction (Burmeister et al., 2013). However, this study discovered that 41% of
overweight and obese study participants met the criteria for food addiction as identified
by the Yale Food Addiction Scale. These new and surprising findings are also confirmed
by a recent study conducted by Schulte et al. (2019). Schulte’s et al. (2019) study delved
deeper into food addiction research and found that only 14.6% of the recruited sample (n
= 501) met the criteria for food addiction. Once Schulte et al. (2019) conducted the study,
38.6% (n = 17) of their study participants (n = 44) met the criteria for food addiction as
identified by the Yale Food Addiction Scale.

166
Implications
There are three areas of potential impact for positive social change at the
individual and societal level. At an individual level, this study shares valuable insight into
the potentially positive role and influence components of social cognitive theory can have
on food addiction and food addiction symptoms. This study also takes a unique approach
to reach individuals by delivering behaviorally based health information digitally. Naslun
et al. (2017) acknowledged that despite empirical evidence demonstrating that
interventions based on behaviorally based theories are more successful than interventions
that are not based on behaviorally based theories few interventions have delved into
digital technologies to target health behaviors. At a societal level, this study sheds light
on the common misconception that being overweight and obese is exclusively due to
“calories in calories out.” This study provides insight into the psychosocial aspect of
addressing food addiction and food addiction symptoms. Finally, there is a
methodological implication as it relates to potential selection bias. This potential
selection bias is due to the possibility of the study participant’s willingness to enroll in a
study of this nature may be different from the general population.
Conclusion
Over 70% of Americans are overweight or obese and those that suffer from being
overweight or obese experience direct and indirect healthcare costs as high as $147
billion (Fortuna, 2012, Center for Disease Control and Prevention, 2013). These indirect
and direct costs are attributed to but not limited to healthcare expenditures for diseases

167
and disabilities that are related to obesity (Rappange, Brouwer, Hoogenveen, & Van
Baal, 2009).
Highly palatable foods such as ice cream, cakes, and various fast foods are linked
to the food additives MSG and HFCS, Napoli (2008). Although they make these foods
taste more appealing, for those that are overweight or obese their brains are more
vulnerable to the addictive effects of these ingredients. This vulnerability results in
experiencing an inability to regulate one’s eating behavior which results in food cravings
and overeating (Blaylock, 1999; Joranby et al., 2005).
This study sought to help those that are overweight and obese by designing an
online quasi-experiment that would utilize components of Bandura’s social cognitive
theory to address food addiction and food addiction symptoms. I compared the effects of
social cognitive theory-based health information with non- social cognitive theory-based
health information on food addiction and food addiction symptoms among obese and
overweight women throughout four weeks. The results of this experiment show that after
controlling for the pre-test, there were no significant differences between the groups.
However, the additional analysis yielded statistically significant results and a strong
correlation to the health information affecting food addiction symptoms. This positive
outcome is an indication that more research should be conducted to explore potentially
more significant findings.

168
References
Adobe Presenter 11.1 [eLearning Computer software]. (2018). Retrieved from
https://www.adobe.com/products/presenter.html
American Psychiatric Association. (2000). Diagnostic and statistical manual of mental
disorders (4th ed. text revision). Washington, DC: Author.
Anderson, E. S., Wojcik, J. R., Winett, R. A., & Williams, D. M. (2006). Social-cognitive
determinants of physical activity: The influence of social support, self-efficacy,
outcome expectations, and self-regulation among participants in a church-based
health promotion study. Health Psychology-Hillsdale Then Washington DC,
25(4), 510. Retrieved from https://search-ebscohost-
com.ezp.waldenulibrary.org/login.aspx?direct=true&db=edsovi&AN=edsovi.000
03615.200607000.00008&site=eds-live&scope=site
Appelhans, B. M., French, S. A., Pagoto, S. L., & Sherwood, N. E. (2016). Managing
temptation in obesity treatment: A neurobehavioral model of intervention
strategies. Appetite, 96, 268-279. https://doi-
org.ezp.waldenulibrary.org/10.1016/j.appet.2015.09.035
Avena, N. M., Bocarsly, M. E., Rada, P., Kim, A., & Hoebel, B. G. (2008). After daily
bingeing on a sucrose solution, food deprivation induces anxiety and accumbens
dopamine/acetylcholine imbalance. Physiology & Behavior, 94(3), 309-315.
doi:10.1016/j.physbeh.2008.01.008
Bandura, A. (1969). Strategies of attitude change. In (S.U.) Principles of behavior
modification (pp. 599). New York, NY: Holt, Rinehart, and Winston, Inc.

169
Bandura, A. (1986). Social foundations of thought and action: A social cognitive theory.
Englewood Cliffs, NJ: Prentice-Hall.
Bandura, A. (1997). The nature and structure of self-efficacy. Self-efficacy: The exercise
of control (pp. 36-79). New York, NY: W.H. Freeman and Company.
Bandura, A. (2004). Health promotion by social cognitive means. Health Information &
Behavior, 31(2), 143-164. doi:10.1177/1090198104263660
Bandura, A. (2007). Much ado over a faulty conception of perceived self-efficacy
grounded in faulty experimentation. Journal of Social and Clinical Psychology,
26(6), 641-658. doi:10.1521/jscp.2007.26.6.641
Bandura, A., Barbaranelli, C., Caprara, G. V., & Pastorelli, C. (2001). Self‐efficacy
beliefs as shapers of children’s aspirations and career trajectories. Child
Development, 72(1), 187-206. doi:10.1111/1467-8624.00273
Bandura, A., & Locke, E. A. (2003). Negative self-efficacy and goal effects revisited.
Journal of Applied Psychology, 88(1), 87. https://doi-
org.ezp.waldenulibrary.org/10.1037/0021-9010.88.1.87
Barrett, D. M., Beaulieu, J. C., & Shewfelt, R. (2010). Color, flavor, texture, and
nutritional quality of fresh-cut fruits and vegetables: Desirable levels,
instrumental and sensory measurement, and the effects of processing. Critical
Reviews in Food Science and Nutrition, 50(5), 369-389.
doi:10.1080/10408391003626322

170
Barry, D., Clarke, M., & Petry, N. M. (2009). Obesity and its relationship to addictions:
Is overeating a form of addictive behavior? American Journal on Addictions,
18(6), 439-451. doi:10.3109/10550490903205579
Basen-Engquist, K., Carmack, C. L., Li, Y., Brown, J., Jhingran, A., Hughes, D. C.,
Waters, A. (2013). Social-cognitive theory predictors of exercise behavior in
endometrial cancer survivors. Health Psychology, 32(11), 1137.
doi:10.1037/a0031712
Basen-Engquist, K., Carmack, C. L., Perkins, H., Hughes, D., Serice, S., Scruggs, S.,
Waters, A. (2011). Design of the steps to health study of physical activity in
survivors of endometrial cancer: Testing a social cognitive theory
model. Psychology of Sport and Exercise, 12(1), 27-35.
doi:10.1016/j.psychsport.2010.07.010
Bates, T. (2012). Crafting an irresistible email subject line. Chief Marketer. Retrieved
from http://www.accessintel.com/
Bellisle, F. (2008). Experimental studies of food choices and palatability responses in
European subjects exposed to the Umami taste. Asia Pacific Journal of Clinical
Nutrition, 17(S1), 1376-379. Retrieved from
http://apjcn.nhri.org.tw/server/APJCN/17%20Suppl%201//376.pdf
Berndt, N. C., Hayes, A. F., Verboon, P., Lechner, L., Bolman, C., & De Vries, H.
(2013). Self-efficacy mediates the impact of craving on smoking abstinence in
low to moderately anxious patients: Results of a moderated mediation

171
approach. Psychology of Addictive Behaviors, 27(1), 113-124.
doi:10.1037/a0028737
Bersoff, D. N. (2008). Record keeping and fees. Ethical conflicts in psychology (4th ed.)
(p. 22). Washington, DC.
Blaylock, R. (1996). Endocrine effect of excitotoxins: Hormones. Excitotoxins: The Taste
That Kills (Kindle Locations 1572-1573). Health Press NA Inc.. Kindle Edition.
Blaylock, R. (1999). Food additive excitotoxins and degenerative brain disorders. Journal
of American Plastic Surgeon. Retrieved from
http://www.jpands.org/hacienda/article27.html
Blum, K., Gardner, E., Oscar-Berman, M., & Gold, M. (2012). “Liking” and “wanting”
linked to Reward Deficiency Syndrome (RDS): hypothesizing differential
responsivity in brain reward circuitry. Current Pharmaceutical Design, 18(1),
113-118.
Bocarsly, M. E. (2016). Food addiction: Applying substance use disorder criteria and
characteristics to identify instances of addictive-like eating. V. R. Preedy (Eds.),
Neuropathology of drug addictions and Substance misuse (pp. 1008 – 1018). San
Diego: Academic Press.
Bragulat, V., Dzemidzic, M., Bruno, C., Cox, C. A., Talavage, T., Considine, R. V., &
Kareken, D. A. (2010). Food‐related odor probes of brain reward circuits during
hunger: A pilot fMRI study. Obesity, 18(8), 1566-1571. doi: 10.1038/oby.2010.57
Bricker, J. B., Liu, J., Comstock, B. A., Peterson, A. V., Kealey, K. A., & Marek, P. M.
(2010). Social cognitive mediators of adolescent smoking cessation: Results from

172
a large randomized intervention trial. Psychology of Addictive Behaviors, 24(3),
436-445. doi:10.1037/a0019800
Brook, J. S., Lee, J. Y., Finch, S. J., Balka, E. B., & Brook, D. W. (2013). Physical
factors, personal characteristics, and substance use: Associations with obesity.
Substance Abuse, 34(3), 273-276. doi: 10.1080/08897077.2013.770425
Burmeister, J. M., Hinman, N., Koball, A., Hoffmann, D. A., & Carels, R. A. (2013).
Food addiction in adults seeking weight loss treatment. Implications for
psychosocial health and weight loss. Appetite, 60, 103-110.
Burns, R. J., & Rothman, A. J. (2015). Offering variety: A subtle manipulation to
promote healthy food choice throughout the day. Health Psychology, 34(5), 566-
570. doi:10.1037/hea0000164
Burrows, T., Skinner, J., Joyner, M.A., Palmieri, J., Vaughan, K., Gearhardt, A. (2017).
Food addiction in children: Associations with obesity, parental food addiction and
feeding practices. Eating Behaviors, 26, 114-120.
Caamaño, M. C., Ronquillo, D., Kimoto, R., García, O. P., Long, K. Z., & Rosado, J. L.
(2016). Beliefs and motives related to eating and body size: A comparison of
high-BMI and normal-weight young adult women from rural and urban areas in
Mexico. BMC Public Health, 16(1), 1014. doi: 10.1186/s12889-016-3695-4
Can you conquer those cravings? (2014, Oct 20). Leicester Mercury Retrieved from
https://search-proquest-
com.ezp.waldenulibrary.org/docview/1614138946?accountid=14872

173
Center for Disease Control and Prevention. (2015). About adult BMI. Retrieved from
http://www.cdc.gov/healthyweight/assessing/bmi/adult_bmi/index.html
Center for Disease Control and Prevention. (2013). Adult obesity facts. Retrieved from
http://www.cdc.gov/obesity/data/adult.html
Center for Disease Control and Prevention. (2014). Healthy Weight - it’s not a diet, it’s a
lifestyle! Retrieved from http://www.cdc.gov/healthyweight/assessing/index.html
Challem, J. (2014). Addiction & nutrition. Better Nutrition, 76(6), 44-48.
Chao, A. M., Shaw, J. A., Pearl, R. L., Alamuddin, N., Hopkins, C. M., Bakizada, Z. M.,
. . . Wadden, T. A. (2017). Prevalence and psychosocial correlates of food
addiction in persons with obesity seeking weight reduction. Comprehensive
Psychiatry, 73, 97-104.
Chaput, J., Klingenberg, L., Astrup, A., & Sjödin, A. (2011). Modern sedentary activities
promote overconsumption of food in our current obesogenic environment. Obesity
Reviews: An Official Journal of the International Association for the Study of
Obesity, 12(5), e12-e20. doi:10.1111/j.1467-789X.2010.00772.x
Clark, M. M., Abrams, D. B., Niaura, R. S., Eaton, C. A., & Rossi, J. S. (1991). Self-
efficacy in weight management. Journal of Consulting and Clinical Psychology,
59(5), 739-744. doi: 10.1037/0022-006X.59.5.739
Clark, P. J. (1956). The heritability of certain anthropometric characters as ascertained
from measurements of twins. American Journal Of Human Genetics, 8(1), 49–54.
Retrieved from https://search-ebscohost-

174
com.ezp.waldenulibrary.org/login.aspx?direct=true&db=mnh&AN=13302199&si
te=eds-live&scope=site
Collison, K., Maqbool, Z., Inglis, A., Makhoul, N., Saleh, S., Bakheet, R., & ... Al-
Mohanna, F. (2010). Effect of dietary monosodium glutamate on HFCS-induced
hepatic steatosis: expression profiles in the liver and visceral fat. Obesity, 18(6),
1122-1134 13p. doi:10.1038/oby.2009.502
Colombi, A. M., & Wood, G. C. (2011). Obesity in the Workplace: Impact on
Cardiovascular Disease, Cost, and Utilization of Care. American Health & Drug
Benefits, 4(5), 271-277.
Comings, D. E., & Blum, K. (2000). Reward deficiency syndrome: Genetic aspects of
behavioral disorders. Progress in Brain Tesearch, 126, 325-341. doi:
10.1016/S0079-6123(00)26022-6
Connor, J. P., Gullo, M. J., Feeney, G. X., Kavanagh, D. J., & Young, R. M. (2014). The
relationship between cannabis outcome expectancies and cannabis refusal self-
efficacy in a treatment population. Addiction, 109(1), 111-119. doi:
10.1111/add.12366
Connor-Greene, P. A. (1993). The therapeutic context: Preconditions for change in
psychotherapy. Psychotherapy: Theory, Research, Practice, Training, 30(3), 375-
382. doi:10.1037/0033-3204.30.3.375
Costantini, V. A., Vicentini, E., Sabbatini, F. M., Valerio, E., Lepore, S., Tessari, M., &
... Corsi, M. (2011). GSK1614343, a novel ghrelin receptor antagonist, produces

175
an unexpected increase of food intake and body weight in rodents and dogs.
Neuroendocrinology, 94(2), 158-168. doi:10.1159/000328968
Campbell, D., Stanley, J. (1963). Sources of invalidity for quasi-experimental designs 7
through 12. Experimental and quasi-experimental designs for research. Boston,
MA: Houghton Mifflin Company
Creswell, J. (2009). Research design, qualitative, quantitative, and mixed methods
approaches (3rd ed.). Los Angeles, CA: Sage Publications.
Darbandi, M., Darbandi, S., Ghayor Mobarhan, M., Akbar Owji, A., Zhao, B., Iraji, K., &
... Mokarram, P. (2012). Effects of auricular acupressure combined with low-
calorie diet on the leptin hormone in obese and overweight Iranian
individuals. Acupuncture in Medicine, 30(3), 208-213. doi:10.1136/acupmed-
2011-010121
Davern, M. (2013). Nonresponse rates are a problematic indicator of nonresponse bias in
survey research. Health Services Research, 48(3), 905-912. doi:10.1111/1475-
6773.12070
Davis, C., Curtis, C., Levitan, R., Carter, J., Kaplan, A., & Kennedy, J. (2011). Evidence
that ‘food addiction’ is a valid phenotype of obesity. Appetite, 57(3), 711-717.
doi: 10.1016/j.appet.2011.08.017
Dennis, K., Tomoyasu, N., McCrone, S., Goldberg, A., Bunyard, L., & Qi, B. (2001).
Self-efficacy targeted treatments for weight loss in postmenopausal
women. Scholarly Inquiry For Nursing Practice,15(3), 259-276

176
Dickerson, F. B., Savage, C. L., Schweinfurth, L. A., Medoff, D. R., Goldberg, R. W.,
Bennett, M., ... & DiClemente, C. (2016). The use of peer mentors to enhance a
smoking cessation intervention for persons with serious mental illnesses.
Psychiatric Rehabilitation Journal, 39(1), 5. doi: 10.1037/prj0000161
Dijkstra, A., & Bos, C. (2015). The effects of repeated exposure to graphic fear appeals
on cigarette packages: A field experiment. Psychology of Addictive
Behaviors, 29(1), 82.
Dinwiddie, S. H., M.D., & Cloninger, C. R. (1991). Family and adoption studies in
alcoholism and drug addiction. Psychiatric Annals, 21(4), 206-208,211-214.
Driscoll, T. J. (1994). Food addiction. New Jersey Nurse, 25(1), 4-4.
Eyres, S. L., Turner, A. I., Nowson, C. A., & Torres, S. J. (2014). Does diet-induced
weight change effect anxiety in overweight and obese adults?. Nutrition, 30(1),
10-15. doi:10.1016/j.nut.2013.05.028
Faul, F., Erdfelder, E., Lang, A.G., & Buchner, A. (2007). G*Power 3: A flexible
statistical Power analysis program for the social, behavioral, and biomedical
sciences. Behavior Research Methods, 39(2), 175-191.
Findparticipants.com (2019). Participant statistics. Retrieved from
https://www.findparticipants.com/participant-statistics
Fiszer, U., Michałowska, M., Baranowska, B., Wolińska-Witort, E., Jeske, W., Jethon,
M., & ... Marcinowska-Suchowierska, E. (2010). Leptin and ghrelin
concentrations and weight loss in Parkinson’s disease. Acta Neurologica
Scandinavica, 121(4), 230-236. doi:10.1111/j.1600-0404.2009.01185.x

177
Forshee, R. A., Storey, M. L., Allison, D. B., Glinsmann, W. H., & al, e. (2007). A
critical examination of the evidence relating high fructose corn syrup and weight
gain. Critical Reviews in Food Science and Nutrition, 47(6), 561-82.
Fortuna, J. L. (2012). The obesity epidemic and food addiction: Clinical similarities to
drug dependence. Journal of Psychoactive Drugs, 44(1), 56-63.
doi:10.1080/02791072.2012.662092
Frankfort-Nachmias, C., & Nachmias, D. (2008). Sampling and sample designs.
Research methods in the social sciences. (7th ed.).. New York, NY: Worth
Publishers.
Frederick, D. A., Saguy, A. C., Gruys, K. (2016). Culture, health, and bigotry: How
exposure to cultural accounts of fatness shape attitudes about health risk, health
policies, and weight-based prejudice. In Social Science & Medicine, 165(2017),
271-279.
Fulton, H. G., Krank, M. D., & Stewart, S. H. (2012). Outcome expectancy liking: A self-
generated, self-coded measure predicts adolescent substance use
trajectories. Psychology Of Addictive Behaviors, 26(4), 870-879.
doi:10.1037/a0030354
Gaby, A. R. (2005). Adverse effects of dietary fructose. Alternative Medicine Review,
10(4), 294.
Gearhardt, A. N., Corbin, W. R., & Brownell, K. D. (2009). Preliminary validation of the
Yale food addiction scale. Appetite, 52(2), 430-436. doi:
10.1016/j.appet.2008.12.003

178
Gearhardt, A. N., White, M. A., Masheb, R. M., Morgan, P. T., Crosby, R. D., & Grilo,
C. M. (2012). An examination of the food addiction construct in obese patients
with binge eating disorder. International Journal of Eating Disorders, 45(5), 657-
663.
George, J., Klika, A., Navale, S., Newman, J., Barsoum, W., Higuera, C., & ... Higuera,
C. A. (2017). Obesity Epidemic: Is Its Impact on Total Joint Arthroplasty
Underestimated? An Analysis of National Trends. Clinical Orthopaedics &
Related Research, 475(7), 1798-1806. doi:10.1007/s11999-016-5222-4
Gibson, C. D., Carnell, S., Ochner, C. N., & Geliebter, A. (2010). Neuroimaging, gut
peptides and obesity: Novel studies of the neurobiology of appetite. Journal of
Neuroendocrinology, 22(8), 833-845. doi: 10.1016/j.physbeh.2010.04.032
Glanz, K., Rimer, B. K., Viswanath, K. (2008). How individuals, environments, and
health behaviors interact – Social cognitive theory. Health behavior and health
information (p. 170). San Francisco, CA: Jossey-Bass.
Göbel, ,C.H., Tronnier, V. M., & Münte, ,T.F. (2017). Brain stimulation in
obesity.International Journal of Obesity, 41(12), 1721-1727.
Goode, H. (2016). Obesity - A Modern, Mismanaged & Misunderstood Malady. Positive
Health, (232), 7
Goossens, L., Braet, C., Van Vlierberghe, L., & Mels, S. (2009). Loss of control over
eating in overweight youngsters: the role of anxiety, depression and emotional
eating. European Eating Disorders Review, 17(1), 68-78. doi: 10.1002/erv.892

179
Gorin, A. A., Powers, T. A., Koestner, R., Wing, R. R., & Raynor, H. A. (2014).
Autonomy support, self-regulation, and weight loss. Health Psychology, 33(4),
332-339. doi:10.1037/a0032586
Gorin, A., Raynor, H., Fava, J., Maguire, K., Robichaud, E., Trautvetter, J., & ... Wing,
R. (2013). Randomized Controlled Trial of a Comprehensive Home Environment-
Focused Weight-Loss Program for Adults. Health Psychology, 32(2), 128-137
Green, S. B., Salkind, N. J. (2011). Independent-samples t test. Jeff Marshall (Eds.),
Using SPSS for windows and macintosh: Analyzing and understanding data. (p.
175). New Jersey: Prentice Hall
Groves, R.M., Fowler, F. F., Couper, M.P., Lepkowski, J.M., Singer, E., & Tourangeau,
R. (2009). Using multiple modes of data collection. Survey Methodology. New
Jersey: Wiley. Kindle e-book.
Gucciardi, A. (2011, November), Addictive as cocaine, fructose fuels cancer and obesity
as American ciet staple. Infowars.com. Retrieved from
http://www.infowars.com/addictive-as-cocaine-fructose-fuels-cancer-and-obesity-
as-american-diet-staple/
Gulliver, S. B., Cammarata, C. M., Leto, F., Ostiguy, W. J., Flynn, E. J., Carpenter, G. J.,
& ... Kimbrel, N. A. (2016). Project Reach Out: A training program to increase
behavioral health utilization among professional firefighters. International
Journal of Stress Management, 23(1), 65-83. doi:10.1037/a0039731

180
Greenway, F. L. (2015). Physiological adaptations to weight loss and factors favouring
weight regain. International Journal Of Obesity (2005), 39(8), 1188-1196.
doi:10.1038/ijo.2015.59
Gregory S., B., I. Sadaf, F., & Stephen, O. (2000). Genetics of body-weight
regulation. Nature, (6778), 644. Retrieved from https://search-ebscohost-
com.ezp.waldenulibrary.org/login.aspx?direct=true&db=edsovi&AN=edsovi.000
06056.200004060.00040&site=eds-live&scope=site
Hardman, C. A., Rogers, P. J., Dallas, R., Scott, J., Ruddock, H. K., & Robinson, E.
(2015). “Food addiction is real”. The effects of exposure to this message on self-
diagnosed food addiction and eating behavior. Appetite, 91, 179-184.
doi:10.1016/j.appet.2015.04.052
Hardy, R., Fani, N., Jovanovic, T., Michopoulos, V. (2018). Food addiction and
substance addiction in women: Common clinical characteristics. Appetite, 120,
367-373.
He, K., Zhao, L., Daviglus, M. L., Dyer, A. R., Horn, L., Garside, D., ... & Stamler, J.
(2008). Association of monosodium glutamate intake with overweight in Chinese
adults: the INTERMAP Study. Obesity, 16(8), 1875-1880.
Hebebrand, J., Albayrak, Ö., Adan, R., Antel, J., Dieguez, C., de Jong, J., & ... Dickson,
S. L. (2014). “Eating addiction”, rather than “food addiction”, better captures
addictive-like eating behavior. Neuroscience And Biobehavioral Reviews, 47295-
306. doi:10.1016/j.neubiorev.2014.08.016

181
Heydari, A., Dashtgard, A., & Moghadam, Z. E. (2014). The effect of Bandura’s social
cognitive theory implementation on addiction quitting of clients referred to
addiction quitting clinics. Iranian Journal of Nursing & Midwifery
Research, 19(1), 19-23. PMCID: PMC3917180
Hintz, S., Frazier, P. A., & Meredith, L. (2015). Evaluating an online stress management
intervention for college students. Journal of Counseling Psychology, 62(2), 137-
147. doi: 10.1037/cou0000014
Hogan, B. E., Linden, W., & Najarian, B. (2002). Social support interventions: Do they
work? Clinical Psychology Review, 22(3), 381–440. https://doi-
org.ezp.waldenulibrary.org/10.1016/S0272-7358(01)00102-7
Hopkinson, J. B. (2016). Food connections: A qualitative exploratory study of weight-
and eating-related distress in families affected by advanced cancer. European
Journal Of Oncology Nursing: The Official Journal Of European Oncology
Nursing Society, 2087-96. doi:10.1016/j.ejon.2015.06.002
Ince, M. L. (2008). Use of a social cognitive theory-based physical-activity intervention
on health-promoting behaviors of university students. Perceptual and Motor
Skills, 107, 833– 836. doi: 10.2466/pms.107.3.833-836
Insawang, T., Selmi, C., Cha’on, U., Pethlert, S., Yongvanit, P., Areejitranusorn, P., & ...
Hammock, B. D. (2012). Monosodium glutamate (MSG) intake is associated with
the prevalence of metabolic syndrome in a rural Thai population. Nutrition &
Metabolism, 9(1), 50-55. doi:10.1186/1743-7075-9-50

182
Johns, G., & Miraglia, M. (2015). The reliability, validity, and accuracy of self-reported
absenteeism from work: A meta-analysis. Journal of Occupational Health
Psychology, 20(1), 1-14. doi:10.1037/a0037754
Johnson, R. J., Gower, T., & Gollub, E. (2009). The sugar fix: The high-fructose fallout
that is making you fat. Simon and Schuster. Rodale - A. Kindle Edition.
Joranby, L., Pineda, K. F., & Gold, M. S. (2005). Addiction to food and brain reward
systems. Sexual Addiction & Compulsivity, 12(2-3), 201-217. doi:
10.1080/10720160500203765
Kelly, J. F., & Greene, M. C. (2014). Where there’s a will there’s a way: A longitudinal
investigation of the interplay between recovery motivation and self-efficacy in
predicting treatment outcome. Psychology of Addictive Behaviors, 28(3), 928-934.
doi:10.1037/a0034727
Kemps, E., Tiggemann, M., & Grigg, M. (2008). Food cravings consume limited
cognitive resources. Journal of Experimental Psychology: Applied, 14(3), 247.
doi: 10.1037/a0012736
Kelly, J. F., & Greene, M. C. (2014). Where there’s a will there’s a way: A longitudinal
investigation of the interplay between recovery motivation and self-efficacy in
predicting treatment outcome. Psychology Of Addictive Behaviors, 28(3), 928-
934. doi:10.1037/a0034727
Kenny, P. (2013). The food addiction. Scientific American, 309(3), 44-49.
Kiernan, M., Brown, S. D., Schoffman, D. E., Lee, K., King, A. C., Taylor, C., & ... Perri,
M. G. (2013). Promoting healthy weight with “stability skills first”: A randomized

183
trial. Journal of Consulting and Clinical Psychology, 81(2), 336-346.
doi:10.1037/a0030544
King, B. M. (2013). The modern obesity epidemic, ancestral hunter-gatherers, and the
sensory/reward control of food intake. American Psychologist, 68(2), 88-96.
doi:10.1037/a0030684
Kinsella, M. (2017). Fostering client autonomy in addiction rehabilitative practice: The
role of therapeutic ‘presence’. Journal Of Theoretical And Philosophical
Psychology, 37(2), 91-108. doi:10.1037/teo0000056
Kinzie, M. B. (2005). Instructional design strategies for health behavior change. Patient
Education and Counseling, 56(1), 3-15. doi 10.1016/j.pec.2004.02.005
Korn, C. W., Rosenblau, G., Rodriguez Buritica, J. M., & Heekeren, H. R. (2016).
Performance feedback processing is positively biased as predicted by attribution
theory. PlosONE, 11(2),
Lanyon, R. I., & Wershba, R. E. (2013). The effect of underreporting response bias on
the assessment of psychopathology. Psychological Assessment, 25(2), 331-338.
doi:10.1037/a0030914
Leahey, T., Bond, D. S., Raynor, H., Roye, D., Vithiananthan, S., Ryder, B., Sax, H.,
Wing, R. (2012). Effects of bariatric surgery on food cravings: do food cravings
and the consumption of craved foods “normalize” after surgery? In Surgery for
Obesity and Related Diseases, 8(1), 84-91
Lee, U. (2003). Panel attrition in survey data: A literature review. (Report No. 41).
Retrieved from http://www.uct.ac.za/depts/cssr/pubs.html

184
Lent, M. R., Eichen, D. M., Goldbacher, E., Wadden, T. A., & Foster, G. D. (2014).
Relationship of food addiction to weight loss and attrition during obesity
treatment. Obesity, 22(1), 52-55. doi: 10.1002/oby.20512
Lenz, L. (2007). FOOD POISONING: MSG linked to obesity is put into a wide range of
foods. CCPA Monitor, 13, 12-13.
Liebman, B. (2012). Food and addiction: Can some foods hijack the brain. Nutrition
Action Healthletter, 39(4), 1-7.
Lochrie, A. S., Wysocki, T., Hossain, J., Milkes, A., Antal, H., Buckloh, L., & ... Lang, J.
(2013). The effects of a family-based intervention (FBI) for overweight/obese
children on health and psychological functioning. Clinical Practice in Pediatric
Psychology,1(2), 159-170. doi:10.1037/cpp0000020
Lowndes, J., Kawiecki, D., Pardo, S., Nguyen, V., Melanson, K., Yu, Z., & Rippe, J.
(2012). The effects of four hypocaloric diets containing different levels of sucrose
or high fructose corn syrup on weight loss and related parameters. Nutrition
Journal, 11(1), 55. doi:10.1186/1475-2891-11-55
Ludman, E., Simon, G. E., Ichikawa, L. E., Operskalski, B. H., Arterburn, D., Linde, J.
A., & ... Finch, E. A. (2010). Does depression reduce the effectiveness of
behavioral weight loss treatment?. Behavioral Medicine (Washington,
D.C.), 35(4), 126-134. doi:10.1080/08964280903334527
Macchi, C. R., Russell, C., & White, M. (2013). Shifting processes model: A conceptual
model for sustainable weight management. Families, Systems, & Health, 31(4),
326-337. doi:10.1037/a0033521

185
Mara, C. A., Cribbie, R. A., Flora, D. B., LaBrish, C., Mills, L., & Fiksenbaum, L.
(2012). An improved model for evaluating change in randomized pre-test,
posttest, follow-up designs. Methodology: European Journal of Research
Methods for the Behavioral and Social Sciences, 8(3), 97-103. doi:10.1027/1614-
2241/a000041
Martin, C. K., O’Neil, P. M., & Pawlow, L. (2006). Changes in food cravings during low-
calorie and very-low-calorie diets. Obesity, 14, 115–121.
Martin, L. F., Hunter, S. M., Lauve, R. M., & O’Leary, J. P. (1995). Severe obesity:
expensive to society, frustrating to treat, but important to confront. Southern
Medical Journal, 88(9), 895-902.
Martinotti, G., Montemitro, C., Baroni, G., Andreoli, S., Alimonti, F., Di Nicola, M., &
... Janiri, L. (2017). Relationship between craving and plasma leptin
concentrations in patients with cocaine
addiction. Psychoneuroendocrinology, 8535-41.
doi:10.1016/j.psyneuen.2017.08.004
Mason, A. E., Lustig, R. H., Brown, R. R., Acree, M., Bacchetti, P., Moran, P. J., ... &
Daubenmier, J. (2015). Acute responses to opioidergic blockade as a biomarker of
hedonic eating among obese women enrolled in a mindfulness-based weight loss
intervention trial. Appetite, 91, 311-320.
McCabe, B. E., Plotnikoff, R. C., Dewar, D. L., Collins, C. E., & Lubans, D. R. (2015).
Social cognitive mediators of dietary behavior change in adolescent

