


African American College Students’ Attitudes
Toward Help Seeking for Mental Health Illness
Chapter 1: Introduction to the Study
Introduction
African Americans encounter higher levels of mental illness stigma (i.e.,
prejudice, discrimination) compared to individuals in other racial/ethnic groups (Ciftci,
Corrigan, & Jones, 2012; Kranke, Guada, Kranke, & Floersch, 2012). Compared to
individuals of mixed race backgrounds and Whites, African Americans diagnosed with
mental illness have lower rates of outpatient mental health services (Substance Abuse
and Mental Health Services Administration, 2015; Ward, Clark, & Heidrich, 2009; Ward,
Wiltshire, Detry, & Brown, 2013; Watson & Hunter, 2015). According to the Substance
Abuse and Mental Health Services Administration [SAMSHA, 2015], the prior year
reported rates for use of mental health services for adults in the United States from
various ethnic/racial groups were as follows: 8.8% for individuals of multiple/mixed
races, 7.8% for Whites, 7.7% for American Indian or Alaska Natives, 4.7% for Blacks,
3.5% for Hispanics, and 2.5% for Asians.
Researchers have indicated that African American college students experience as
much mental distress as students in other ethnic groups; however, they are less likely to
use psychological services from professional mental health sources (Avent, Cashwell, &
Brown‐Jeffy, 2015; Masuda et al., 2009; Masuda, Anderson, & Edmonds, 2012;
Villatoro & Aneshensel, 2014). Stigmas against mental health present a major barrier to

seeking treatment or ongoing treatment participation for African American college
students (Songtag-Padilla et al., 2014). This study is of relevance as more work is needed
to examine the complex relationships between stigma against mental health, ethnic
identity, and help-seeking among African American college students (Alvidrez,
Snowden, &
Patel, 2010; Villatoro & Aneshensel, 2014; Vinson, Crowther, Austin, & Guin, 2014).
Results from this study may have a few implications for social change. Results
from this study can contribute information regarding the relationships between mental
health stigmas and help seeking for mental illness among African American college
students attending Historically Black Colleges and Universities (HBCUs). University
school counselors and social workers could use the information to support the need for
the developing gender-based mental health awareness campaigns and seminars that
provide information about mental health services for African American college age
students. The campus-based mental health awareness campaigns and seminars could
address ways to maintain a decrease in stigmas towards mental illness, inform students
about the availability of campus mental health services, and explain the benefits that
could be obtained from using those services. This type of social change can initially be
implemented by the student members, faculty, and administrators taking the lead to
spread awareness and joining social advocacy groups like National Alliance on Mental
Illness, (NAMI) who already have the tools needed to connect with communities and
organizations.

In this dissertation, I present a brief depiction of the literature that addresses the
impact of mental health stigmas and help-seeking behavior among African American
college students. I further address how ethnic identity may be related to one’s attitude
toward seeking treatment for a mental illness. I also discuss the prevalence of mental
health illness and then focus on the topic of stigma of mental health, the effects of stigma
against mental health, and attitudes and help-seeking behaviors of individuals diagnosed
with mental health illness. In addition, I include literature on the modified labeling theory
as the theoretical framework for this study. The research questions, hypotheses, as well
as limitations in this research are also identified in this section.
Background
Researchers have indicated that in any given year, an estimated 13 million
American adults (approximately 1 in 17) have a serious debilitating mental illness, and
one in five adults experience a less serious mental condition each year (Alvidrez et al.,
2010; Nordberg, Hayes, McAleavey, Castonguay, & Locke, 2013; Sosulski &
Woodward, 2013; Turner, Wildschut, Sedikides, & Gheorghiu, 2013). However, more
than 70% of adults with diagnosed mental illnesses do not receive healthcare services of
any kind, and only 13% of individuals who do seek mental health treatment seek help
from a mental health professional (Nordberg et al., 2013). The percentage of young
adults aged 18 to 25 years diagnosed with any mental illness who received mental health
treatment (35.1%) was lower than adults aged 26 to 49 years (43.1%) and adults aged 50
and older (46.8%; National Institute of Mental Health, 2017). Furthermore, more women

diagnosed with a mental disorder (48.8%) received mental health treatment in
comparison to men (33.9%; National Institute of Mental Health, 2017).
Prevalence of Mental Health Disorders
Mental health disorders are health conditions that are characterized by alterations
in thinking and mood (Nordberg et al., 2013). Mental illness adversely affects one’s
concentration, motivation, emotional health, and academic success (Salzer, 2012).
Mental health disorders can negatively impact one’s behavior, which could further lead
to distress or impaired functioning (Corrigan, Druss, & Perlick, 2014; Nordberg et al.,
2013). Half of mental health conditions begin by age 14, and 75% of mental health
conditions develop by age 24 (McKinney, 2009; National Alliance on Mental Health,
n.d.). The most likely period for a person to seek professional help is 6 to 23 years after
experiencing the first symptoms (Jennings et al., 2015; Kosyluk et al., 2016; McKinney,
2009).
Mental Illness Among College Students
Mental illness among college students is a public health concern as past research
has revealed that almost half of college students between the ages of 18 and 24 years
have been diagnosed with a psychiatric disorder, and 4% have been diagnosed with a
serious mental illness (Bonnie, Stroud, & Breiner, 2015; Hayes et al., 2011; Huynh &
Fuligni, 2012). Other researchers have indicated that two-thirds of individuals diagnosed
with mental illness and almost half of those with a serious mental illness did not receive
mental health treatment (Bonnie et al., 2015). Despite the prevalence of mental illness
among college students, results from several studies revealed that the treatment-seeking

rate for mental illness was low among college students. For instance, 32% of college
students experienced symptoms consistent with a mental health diagnosis, and, of those,
64% did not receive mental health services (Eisenberg, Hunt, Speer, & Zivin, 2011;
Nordberg et al., 2013; Pedrelli, Nyer, Yeung, Zulauf, & Wilens, 2015). Other researchers
found that close to 66% of college students with mood disorders did not receive mental
health services for their problems (Hayes et al., 2011; Nordberg et al., 2013). In addition,
even when mental health services are available on campuses, Marsh and Wilcoxon
(2015) reported that less than half of students with mental health needs used mental
health services.
Barriers to Help Seeking for Mental Illness
Many college students do not seek treatment for mental illness because of barriers
such as financial constraints, concerns about confidentiality, and stigmas against mental
illness (Eisenberg, Golberstein, & Gollust, 2007; Schoen & McKelley, 2012). Lack of
awareness of university mental health services has also been identified as a barrier to
college students seeking treatment for mental health issues (Kranke, Jackson, Floersch,
Townsend, & Anderson-Fye, 2013). In addition, socioeconomic and psychosocial factors
such as poverty, lack of access to transportation, ethnicity of mental health professionals,
and mistrust of mental health care providers are other barriers as to why students do not
seek treatment for mental health concerns (Masuda et al., 2012; Nam, Choi & Lee,
2015). Several researchers have reported that students frequently cited fear of
stigma as a primary deterrent to their seeking treatment for mental illness (Aegisdottir,
O’Heron,

Hartong, Haynes, & Linville, 2011; Hardy et al., 2011; Hayes et al., 2011; Zellmann,
Madden, & Aguiniga, 2014). Other barriers to treatment seeking included the expectation
of discrimination against people diagnosed with mental illness (Henderson, Evans-
Lacko, & Thornicroft, 2013). Results from studies have also revealed that this stigma
may be related to African Americans’ underuse of mental health services (Ciftci et al.,
2012; Kranke et al., 2013; Masuda et al., 2012; Ward et al., 2013). In addition, racial
ethnic minority students may be hesitant to seek treatment from European American
providers because of factors such as cultural mistrust, peer norms related to self-reliance,
family norms pertaining to privacy, double stigma related to racism and mental illness,
and doubts about the availability of culturally sensitive services (Barksdale & Molock,
2009; Braithwaite, Taylor, & Treadwell, 2009; Hayes et al., 2011; Masuda et al., 2012;
Watson
& Hunter, 2015).
Impact of Mental Illness on College Students
Mental illness has a negative impact on college students’ academic performance.
For instance, results from a national report revealed that 86% of students who had a
psychiatric disorder withdrew from college prior to the completion of their degree (as
cited in Krankie, Jackson, Floersch, Townsend, & Anderson-Fye, 2013). Results from a
national study of mental health among college and university students revealed that
students with mental illness tend to have lower grade point averages than their peers (as
cited in Eisenberg, Golberstein, & Hunt, 2009; Kranke et al., 2013).

Mental Illness and African Americans
Findings from several studies have shown that African Americans experience
mental health concerns at the same rate as their non-Hispanic White counterparts
(Masuda et al., 2012; Ojelade, McCray, Ashby, & Meyers, 2011). However, African
Americans tend to underuse available counseling services compared to other racial
groups (Avent et al., 2015; Buser, 2009; Ojelade et al., 2011; Sosulski & Woodward,
2013; Villatoro & Aneshensel, 2014). An estimated 815,000 African American adults
had a serious mental illness in 2012 (SAMSHA, 2013). However, only half (57.2%) have
received mental health treatment in comparison to 67.4% of non-Hispanic Whites and
69.4% of Whites who received mental health treatment (SAMSHA, 2013). African
Americans experience more severe forms of mental health conditions due to unmet
mental health needs (inability to access mental health services, lack of understanding of
mental health illness, symptoms, and information as to how to prevent mental health
illnesses (U.S. Department of Health and Human Services Office of Minority Mental
Health, 2016). In addition, barriers can include cultural mistrust, stigma, socioeconomic
status, and spiritual beliefs (National Alliance on Mental Illness, n.d.; Ward et al., 2013).
In addition, according to the Health and Human Services Office of Minority Health
(2016), African Americans are also 20% more likely to experience serious mental health
problems than the general population.
Racial and ethnic minority students often encounter additional environmental
stressors that may contribute to the onset of mental illness such as discrimination, racial
tension, and feeling that one’s ethnic group is not valued by society (Avent et al., 2015;

Cheng et al., 2013; Huynh & Fuligni, 2012). These stressors and experiences may further
attribute to cultural distrust, which may inhibit seeking treatment for mental health
issues. Untreated mental health issues may in turn negatively impact students’ health,
wellbeing, and functioning (Eshun & Packer, 2016).
Perceptions of Mental Illness and Help-Seeking Behavior
African American students, overall, could benefit from the promotion of
behavioral health programs on HBCU campuses because such programs could be useful
in alleviating stigmas against seeking treatment for mental illness. It is important for
African American students attending HBCUs to understand how attitudes toward mental
illness, labeling, and stigma are related to treatment avoidance, underuse of mental health
treatment facilities, and poor adherence to physician prescribed medication for treating
mental illness (Conner, 2010); Watson & Hunter, 2015). Information gathered from this
study could assist African American students, their families, policy makers, institutional
leaders, college administration, and campus organizations to develop a better
understanding of how stigmas and labels affect help-seeking behavior for mental illness
(see Gentry, 2014; Walker, 2015). HBCUs play an important role in educating African
American students, and this role could be expanded to promoting awareness of mental
health illness (Gentry, 2014; Walker, 2015). Providing students with the insight and
resources to combat mental illness, labeling, and stigmas against mental illness can
further lead to educational success for some (Walker, 2015). Researchers have further
indicated the need for college administrators to put more effort toward implementing
mental health outreach strategies early on for incoming freshmen students as they enter

college (Clauss‐Ehlers & Parham, 2014; Heitzmann, 2011). Findings from past research
revealed that as college students acquire more information about mental health services,
they may develop more favorable attitudes toward mental health services (Gagnon,
Gelinas, & Friesen, 2017; Katz & Davison, 2014). Outreach strategies include ideas such
as implementing educational workshops, making psychoeducational materials about
mental illness mandatory on campus, providing required freshman orientation classes on
an introduction to maintaining mental health, and partnering with organizations like
Active Minds and Nami for additional tools to use on campus. Colvin, Bullock, and
George (2016) also found that the more awareness and knowledge that African American
students received on mental health issues, the more their help-seeking behavior and
intentions were positively associated with those who were upper classmen in college
(Colvin et al., 2016).
Most studies related to African American college students and mental illness have
focused on assessing help-seeking behavior, the stigma of mental illness, perceptions
and/or attitudes, and the impact of these variables on the African American population in
general (Ashley, 2014; Chandler, 2010; Cokley, Mcclain, Enciso, & Martinez, 2013;
Copeland & Snyder, 2011). Many research studies that have addressed African American
college students have been conducted on majority White campuses that have small
African American student populations (Cheng et al., 2013; Hayes et al., 2009; Hooper,
Wallace, Doehler, & Dantzler, 2012., 2012). I did not find any literature that addressed
the associations between stigmas against mental health illness, attitudes toward mental
illness, help-seeking behavior, and ethnic identity for African American college students

attending HBCUs. I also did not locate any studies that assessed the predictive
relationships for the combination of all four variables within the last 5 years. Researchers
generally recruited participants of mixed ethnicities from predominantly White colleges
in studies or did not specifically focus on ethnic identity as a factor for treatment seeking
behavior. For this reason, the degree to which findings from those studies can generalize
many to larger populations of African American college students is unclear (see Alvidrez
et al., 2010; Fischer et al., 2014).
Ethnic Identity and Individual Behavior
When it comes to African Americans and mental health treatment, other research
has indicated that stigma is a significant mediator of acculturation and attitudes toward
mental health treatment; however, ethnic identity is a significant predictor of intention to
seek counseling (Pasupuleti, 2013). According to Pasupuleti (2013), strong levels of
ethnic identity are related to a greater intention to seek counseling. Researchers have
revealed a positive relationship between strong ethnic identity and positive psychological
outcomes for individuals from diverse racial backgrounds (Cheng et al., 2013; Hooper et
al., 2012). For instance, Lopez, Antoni, Fekete, & Penedo, (2012) reported that ethnic
identity is attributed to individuals’ confidence in their ability to cope with stress. Other
research has shown that ethnic identity was positively related to one’s perception that
people were available to provide emotional and social support to them (Forsyth & Carter,
2012; Lopez et al., 2012). In contrast, results from other studies have revealed that racial
and ethnic minority college students used mental health service less frequently than
nonminority students, and they tended to hold less favorable attitudes toward seeking

professional psychological help (Loya, Reddy, & Hinshaw, 2010; Masuda et al., 2009;
Sosulski & Woodward, 2013).
Ethnic identity has also been associated with less perceived discrimination, fewer
depressive symptoms, less psychological distress, fewer health problems, and better
overall quality of life in minority individuals (Lopez et al., 2012). It is possible that
racial/ethnic minority college students with an achieved ethnic identity may have fewer
concerns about being stigmatized by others and less self-stigma for seeking professional
psychological help (Cheng et al., 2013). However, I did not locate any studies that have
assessed the impact of ethnic identity on individuals’ perceptions of seeking professional
help for mental illness among African American college students attending HBCUs.
Therefore, in this study, I assessed the relationship between the stigma of mental illness,
perceptions, and attitudes of mental illness, help-seeking behavior, and ethnic identity for
African American college students attending HBCUs.
Problem Statement
Mental illness among college students represents a significant public health issue
in the United States. Almost half of college-age individuals have a psychiatric disorder
(Hayes et al., 2011; Lipson, Lattie, & Eisenberg, 2019; Pedersen & Paves, 2014). Mental
illness has a negative impact on college students’ academic performance in terms and
contributes to higher attrition rates (Gentry, 2014; Krankie et al., 2013), and students
with mental illness tend to have lower grade point averages (Eisenberg, Hunt, & Speers,
2013; Krankie et al., 2013; Mojtabai et al., 2015). Data from a national report showed
that 86% of students who had a psychiatric disorder withdrew from college prior to

completion of their degree (as cited in Kranke et al., 2013). Findings from other studies
have linked mental illness to substance abuse, low self-esteem, isolation, reluctance of
self-disclosure, and impaired social relationships (Kobau et al., 2011; Laidlaw,
McLellan, & Ozakinci, 2016; Lyndon et al., 2016; Marsh & Wilcoxon, 2015; Songtag-
Padilla et al., 2014). Researchers have given considerable attention to the lack of
seeking mental health treatment among African American college students (Cheng et al.,
2013; Cheng et al.,
2013, Copeland et al., 2013). A recent survey of college students revealed that 32% of
college students presented symptoms consistent with a mental health diagnosis and that
only 64% of students with symptoms of mental illness received mental health services
(Nordberg et al., 2013). Researchers have revealed that racial and ethnic minority
students have been hesitant to seek mental health treatment because of stigmas related to
racism and mental illness (Cheng et al., 2013; Hardeman et al., 2016; Masuda et al.,
2012). However, I did not locate any studies that have addressed help seeking for mental
health treatment among African American college students attending HBCUs (Cheng et
al., 2013; Cokely et al., 2013; Colvin et al., 2016; Huynh & Fuligni, 2012; Walker,
2015). There was a gap in the literature regarding how ethnic identity and attitudes
toward mental illness have influenced help-seeking behavior related to mental illness
among African American college students (Huynh & Fuligni, 2012; Lopez et al., 2012).
The problem investigated in this study is the degree to which stigma of mental illness,
perceptions of mental illness, and ethnic identity predicts one’s attitude toward help

seeking for mental health among African American college students attending an HBCU
after controlling for gender.
Purpose
The purpose of this quantitative, nonexperimental, correlational study was to
investigate the predictive relationships between ethnic identity, stigma of mental illness,
perceptions of mental illness, and attitudes toward seeking professional help for mental
illness among African American college students after controlling for gender. The
independent variables for this study were ethnic identity, stigma of mental illness, and
perceptions of mental illness. The dependent variable was attitude towards seeking
professional psychological help. Past research revealed that mental illness is associated
with a number of adverse outcomes for college students (Kobau et al., 2011; Marsh &
Wilcoxon, 2015; Songtag-Padilla et al., 2014). Those adverse outcomes include
depression, lowered self-esteem, social isolation, and reluctance to seek help for
treatment (Chronister, 2013; Kranke et al., 2013). Other researchers have documented a
positive relationship between ethnic identity and positive psychological outcomes (Avery
Tonidandel, Thomas, Johnson, & Mack, 2007; Cheng et al., 2013; Hooper et al., 2012). I
conducted this study to assess the relationship with the ethnic identity, perception, and
stigma of mental illness for African American college students attending HBCUs. This
study is relevant as more work is needed to examine the complex relationship between
stigma, ethnic identity, perceptions of mental illness, and help-seeking among African
American college students (see Alvidrez et al., 2010; Villatoro & Aneshensel, 2014;
Vinson et al., 2014).

Research Question and Hypothesis
Research Question: What are the predictive relationships between ethnic identity,
stigmas against mental illness, perceptions of mental illness, and attitudes towards
seeking professional help for mental health issues among African American college
students after controlling for gender?
H0: Ethnic identity (scores on the Multigroup Ethnic Identity Measure), stigma
against mental illness (scores on Self Stigma of Mental Illness), and perceptions of
mental illness (scores on the Attitudes to Mental Illness Questionnaire) are not
statistically significant predictors of attitudes toward help seeking for mental illness
(scores on the Attitudes Toward Seeking Professional Help Scale) of African American
college students attending a HBCU after controlling for gender.
Ha: Ethnic identity (scores on the Multigroup Ethnic Identity Measure), stigma
against mental illness (scores on Self Stigma of Mental Illness), and perceptions of
mental illness (scores on the Attitudes to Mental Illness Questionnaire) are statistically
significant predictors of attitudes toward help seeking for mental illness (scores on the
Attitudes Toward Seeking Professional Help Scale) of African American college students
attending a HBCU after controlling for gender.
The independent variables for this study were ethnic identity, stigma against
mental illness, and perceptions of mental illness. The dependent variable was attitude
towards help seeking. The data were analyzed using a multiple regression analysis.
Statistical Package for the Social Sciences (SPSS) was used to analyze all data collected
for this study.

Theoretical Framework
The theoretical foundation that was used to guide this study was the modified
labeling theory. The labeling theory was first introduced by Becker in 1963. This theory
is based on the view of deviance, which posits that labels lead an individual to engage in
deviant behavior. Those who are labeled are often viewed as being an outsider or
individuals whose behaviors break the rules or norms of a social group (Becker, 1963).
The original labeling theory further asserted that the expectations attached to the label
tend to perpetuate the mental illness (Scheff, 1966).
Modified labeling theory was introduced by Link and associates in 1989, which
was derived from the original labeling theory (Link, Cullen, Struening, & Shrout, 1989).
The modified labeling theory asserts that expectations from being labeled can have
negative effects on individuals (Link et al., 1989; Link & Phelan, 2013; Thoits, 2011).
The modified labeling theory draws on Scheff’s (1966) labeling theory but focuses on the
consequences of labeling rather than on factors that lead to individuals being labeled
(Link & Phelan, 2013). Premises of the modified labeling theory posit that stigmas and
labels associated with having a mental disorder can cause individuals to withdraw from
society, conceal their diagnosis, or refuse to inform others about their mental illness in
order to prevent others from developing negative perceptions about them (Link &
Phelan, 2013; Markowitz, Angell, & Greenberg, 2011). Principles of the modified
labeling theory propose that individuals diagnosed with mental illness may develop
expectations of rejection or that others will devalue them (Granello & Gibbs, 2016;
Kroska, Harkness, Brown, & Thomas, 2015; Thoits, 2016). Premises of the modified

labeling theory can be used to speculate that cultural conceptions and stigmas become
personally relevant to individuals diagnosed with mental illness. In turn, individuals
internalize societal conceptions of what it means to be labeled mentally ill (Link et al.,
1989; Markowits et al., 2011; Thoits, 2011, 2016). Individuals come to anticipate
negative societal reactions to their illness, and consequently, many individuals may
refuse to seek treatment in order to avoid the stigma of being labeled mentally ill (Link et
al, 1989; Thoits, 2011; Markowitz et al., 2011; Szeto, Luong, & Dobson, 2013).
Therefore, the use of modified labeling theory was appropriate for this study because this
theory gave insight into how the label of being stigmatized with a mental illness can
impact a person’s help-seeking behavior.
Nature of the Study
The purpose of this quantitative, nonexperimental, correlational study was to
investigate the predictive relationships between ethnic identity, perceptions of mental
illness, stigma of mental illness, and attitudes toward seeking professional help for
mental illness. The independent variables for this study were ethnic identity, stigma of
mental illness, and perceptions of mental illness. The dependent variable was attitude
towards help seeking. I analyzed the data using a multiple regression analysis. I used a
crosssectional, survey design to assess perceptions of mental illness of African American
college students attending a HBCU in the southeastern United States.
Definitions
Ethnic identity: Refers to the part of self-concept that is derived from knowledge
of an individual’s membership within an ethnic group together with an emotional

significance attached to that membership (Fischer et al., 2014; Tajfel, 1981). Help-
seeking behavior: Help-seeking behavior is defined as behavior directed toward seeking
treatment or counseling for any problem with emotions, nerves, or mental health in any
inpatient or outpatient setting, or the use of medication for treatment of any mental or
emotional condition (Parcesepe & Cabassa, 2013).
Mental health illness: Mental illness among adults is defined as persons aged 18
or older who currently or at any time in the past year have had a diagnosable mental,
behavioral, or emotional disorder resulting in substantial impairment in carrying out
major life activities (Chronister, Chou, & Liao, 2013).
Mental health stigma: Mental health stigma is conceptualized as a set of negative
attitudes toward people with a psychological disorder and beliefs that motivate
individuals to fear, reject, avoid, and discriminate against people with mental illness
(Alvidrez et al., 2010; Corrigan, 2004; Masuda & Latzman, 2011; Parcesepe & Cabassa,
2013).
Public stigma: Pertains to the negative and discriminatory attitudes and behaviors
of society toward people with mental illness who seek mental health service (Corrigan,
2004; Kranke et al., 2012; Nam et al., 2015; Vogel, Wade, & Haake, (2006); Vogel,
Wade, & Hackler, 2007).
Self-stigma: Refers to an individual's negative perceptions about herself or
himself for seeking psychological help (Corrigan & Kleinlein, 2005; Kranke et al., 2012;
Nam et Al., 2015; Vogel et al., 2006; Vogel et al., 2007).

Assumptions
There are several assumptions that were associated with this study. First, I
assumed that there was a limitation of participants wanting to participate in this study due
to the topic of study. In addition, I assumed that all participants would answer the survey
questions honestly knowing that their anonymity and confidentiality would be preserved.
I also assumed that participation would be voluntary. Considering that this is survey
research, I assumed that the variables under investigation (which included ethnic identity,
perception of mental illness, stigma of mental illness, and one’s attitude towards help
seeking) were measurable. I also assumed that the instruments that were used in this
study (Multigroup Ethnic Identity Measure, the Attitudes to Mental Illness
Questionnaire, Self-Stigma of Mental Illness, Attitudes towards Mental Illness
Questionnaire, and the Attitudes Toward Seeking Professional Help Scale) were valid
and reliable measurements for collecting data from college students on the variables of
interested. I addressed the psychometric properties of the instruments that were used to
collect data for this study in Chapter 3. I assumed that because I was using a survey
design, limitations included respondent availability, limited sampling, and the inability to
probe participants.
Scope and Delimitations
The scope of the current study included an exploration of the stigmas,
perceptions, and attitudes toward help-seeking behavior towards mental health illness
among African American college students after controlling for gender. I further
investigated the relationship between ethnic identity and one’s attitude toward

helpseeking behavior towards mental illness. The targeted population of this study was
African American college students attending HBCUs.
For the purpose of this study, the theoretical framework was limited to the
modified labeling theory. Convenience sampling and snowball sampling were used to
recruit African American college students from three HBCUs located in Atlanta, GA.
Participants in this study may not have been representative of all African American
students in the United States, which may have limited the generalizability of the results.
Because this sample was based on college students, their opinions and attitudes may have
been different from those of the general population.
Limitations
The present study had a couple of notable limitations. The present findings were
derived from only three HBCUs in the Atlanta, GA area. This limited data collection
may have limited the generalizability of the results from this study to students attending
other college campuses. The ethnicity of participants was restricted to African
Americans. Respondent availability and limited sampling are limitations in survey
research because participants are limited to those who are available to complete the study
and to those with available time to complete the study (Creswell, 2013). A closed-ended
survey also limited me from gaining insight into participants’ interpretations of each
survey question or answer option provided. I did not investigate other factors that may be
particularly relevant to help-seeking attitudes of African American college students, such
as socioeconomic factors, religious beliefs, trust of the provider, program of study, and

age (see Kranke et al., 2013; Smith & Tremble, 2016; Ward et al., 2013; Watson &
Hunter,
2015).
Significance
This study is significant as it addressed ethnic identity, stigma of mental health,
perceptions of mental illness, and attitudes towards seeking professional help for mental
health among African American college students after controlling for gender. Knowledge
gained from this research could highlight the importance of individuals developing
campus-based programs that promote knowledge and awareness of issues surrounding
help seeking for mental illness for African American college students. Findings from this
study could further be used to advocate the need for promoting awareness of mental
illness through the use of workshops, courses, pamphlets, or through literature that is
made available in campus-based counseling centers. This information could be made
available to all college students in student activity centers, dormitories, counseling
centers, and administration offices. Past studies have shown that undergraduate students
who completed a full semester course on severe mental illness had more positive
attitudes about people with mental illness than students who did not have this course
(Theroit & Ledato, 2012). Results from this study may be of interest to mental health
advocacy groups and national organizations such as Mental Health America of Georgia
(2017) and the National Alliance on Mental Health Illness (n.d.). Both advocacy
organizations are devoted to bringing awareness to the public about the topic of mental
health. Findings from my research could potentially be used to inform advocacy

organizations of the need to bring mental illness awareness campaigns to African
American college students and, specifically, to students on HBCU campuses. The overall
goal of these types of organizations is to reduce the stigma associated with mental illness
in the community and on campuses, while also encouraging people to seek help for
mental health issues
(Mckinney, 2009; Mental Health of America of Georgia, 2017; Nam et al., 2013;
National Alliance on Mental Health, n.d.). By openly addressing stigmas associated with
mental illness, students could possibly begin to learn how to take steps towards breaking
the silence of mental illness. By breaking the silence of mental illness, African American
college students may begin breaking down barriers to seeking professional help and
become actively engaged in treatment for mental health issues.
Summary
Mental illness stigma remains to be a barrier for treatment seeking for not only
college students in general but for African American college students specifically.
Mental illness stigma also impacts the attitudes and beliefs towards mental illness for
African American students. The fear of being stigmatized is the most cited reason
individuals avoid psychotherapy (Cechnicki, Matthias, & Angermeyer, 2011; Chronister
et al., 2013; Vogel, Wade, & Ascheman, 2009). The National Institute of Mental Health
views stigma as the primary barrier that prevents individuals with mental illness from
seeking treatment (McKinney, 2009; Nam et al., 2013; Parcesepe & Cabassa, 2013).
There is also a growing body of research that has revealed that the frequency and severity
of mental health problems on college campuses have increased, and many students do not

seek psychological help (Benton, Robertson, Tseng, Newton, & Benton, 2003; Blanco et
al., 2008; Cheng et al., 2013; Zivin, Eisenberg, Gollust, & Golberstein, 2009). Stigmas
and perceptions associated with mental illness can contribute to a student’s difficulty in
successfully completing college (Huynh & Fuligni, 2012; Schoen & McKelley, 2012).
The public has also largely contributed to the stigmatization of individuals seeking
psychological services, and, as a result, individuals may avoid treatment in order to
reduce the consequences. Reducing the stigma of mental illness involves the
collaboration of college administrators, community leaders, faculty, and students
working together to actively create communication that helps to promote and educate
students about mental illness and the reason individuals avoid psychotherapy (Cechnicki
et al.,
2011; Chronister et al., 2013; Vogel et al., 2009).
In Chapter 2, I present research that addresses the independent variables (i.e.,
stigma of mental illness, perceptions of mental illness, and ethnic identity) and the
dependent variable (help-seeking behavior for mental health treatment). In Chapter 2, I
also highlight the prevalence of mental health and the modified labeling theory as the
theoretical framework.
Chapter 2: Literature Review
Introduction
According to the National Institute of Mental Health, in any given year, an
estimated 13 million American adults have a debilitating mental illness (as cited in
Alvidrez et al., 2010; Kessler et al., 2010; Nordberg et al., 2013). Mental disorders

account for nearly one-half of the disease burden for young adults in the United States
(Eisenberg & Hunt, 2010). According to Kranke et al. (2013), as many as 45% of college
students may meet the criteria for a diagnosis of mental illness. Findings from the
growing body of research have indicated that although the frequency and severity of
mental health problems among students on college campuses have increased, many
students do not seek psychological help (Benton et al., 2003; Blanco et al., 2008; Cheng
et al., 2013; Zartaloudi & Madianos, 2010; Zivin et al., 2009). In particular, African
Americans are less likely to seek psychotherapy, are more likely to terminate therapy
prematurely, and attend fewer treatment sessions (Castro et al., 2015; Masuda et al.,
2012; Sickel, Seacat, & Nabors, 2014).
Although research that addresses African Americans with mental illness has been
increasing, few researchers have addressed how the relationships between the stigma of
mental illness and ethnic identity are related to help-seeking behavior of African
American college students. More work is needed to understand the complex relationship
between stigma against mental illness and help seeking among African American college
students, particularly among students attending racially and culturally supportive schools
such as HBCUs (Alvidrez et al., 2010). The purpose of this study was to examine the
predictive relationship between mental health stigmas, perception of mental illness,
ethnic identity, and attitudes toward seeking treatment for mental health illness among
African American college students enrolled in HBCUs.
In this chapter, I give a brief depiction of the literature on the impact of stigma
and help-seeking behavior for African American college students. Findings from this

research can contribute to the body of literature regarding the impact of ethnic identity as
a variable that impacts one’s attitude toward seeking treatment for a mental illness. In the
literature search section, I give a brief overview of the methodology used in identifying
and accessing library databases for this dissertation. In the literature search strategy
section, I further explain terms, databases, and research components that were taken into
consideration in searching for articles that were relevant to this study. The next section
addresses the theoretical foundation. In this section, I give an overview of the history of
labeling theory and further explain how the modified labeling theory has been used to
further explain the impact of labeling on individuals diagnosed with mental illness. In the
next section, I give an in-depth assessment of past research studies relevant to stigma,
perception of mental illness, one’s ethnic identity, and attitude towards seeking treatment
for mental illness for African American college students attending HBCUs.
Literature Search Strategy
I completed a peer review search for articles on help-seeking attitudes for mental
illness and the stigma of mental illness for traditional age college students from 18 to 24
years of age. I established several rules to determine which articles to include in the
metaanalysis. First, I limited the analysis to studies in which the participants were
university students because the focus of this study was to assess attitudes and how stigma
impacts the use of mental health services in a subsection of the college student
population. The particular subpopulation of interest for this scope of study was African
American college students. I conducted an extensive search of databases, which included
the following: ERIC, PsycINFO, ProQuest, PsycARTICLES, Google Scholar, and

SocINDEX. Some of these databases were accessed using Walden University’s library
search engine and others were identified through Google scholar. I searched for articles
with keywords such as help-seeking attitudes, ATSPPH survey, AMIQ survey, MEIM-R
scale, SSOMI, attitudes toward seeking professional psychological help, self-stigma,
counseling, and counseling services. In addition, I also researched articles using
keywords such as African American college students, African American stigmas toward
mental illness, ethnic identity, HBCUs, help seeking, help-seeking behavior, intention of
seeking counseling, intention to seek counseling services, mental illness, psychotherapy,
seeking behavior, seeking help, and stigma. The search of articles was restricted to
articles published from
2010 to 2019.
Theoretical Framework
The theoretical framework that was used to guide this study was the modified
labeling theory. The modified labeling theory spun out of the work of the labeling theory,
which was originally founded by Becker in 1963. Labeling theory holds that individuals
who have been categorized by other people as deviant come to view themselves as
deviant (Becker, 1963). Link et al. (1989) developed a modified labeling theory that
derived its’ foundation from the original labeling theory (Link & Phelan, 2013), but
stepped away from the claim that labeling was a direct cause of mental illness.
Modified labeling theory was founded in 1966 by Cohen and Scheff (Scheff,
1966). The modified labeling theory draws on premises from labeling theory but focuses
on the consequences of labeling rather than on factors that lead to labeling (Link &

Phelan, 2013; Ray & Dollar, 2014; Scheff, 1966; Thoits, 2011). The modified labeling
theory states that in as much as the labelling theory does not result in mental disorders, it
can still lead to negative outcomes in affected individuals. The modified labeling theory
further implies that being labeled mentally ill somehow leads to a modification of how an
individual views him or herself (Scheff, 1966). This modified view may result in the
individual feeling pressured to conform to a particular view of behavior in order to fit in
with others (Granello & Gibbs, 2016; Kroska et al., 2015). The modified labeling theory
asserts that expectations from being labeled could have a negative effect on individuals
(Scheff, 1966; Link et al., 1989; Ray & Dollar, 2014; Thoits, 2011). Cohen and Scheff
(1966) stated that according to the original labeling theory perspective on mental illness,
the label mentally ill activates negative effects that can result in the social rejection of
individuals. The negative effects include low self-esteem, self-rejection, rejection from
peers, fear, low expectations of self, withdrawal from society, and reluctance to seeking
mental health treatment (Scheff, 1966).
According to premises, modified labeling theory, cultural conceptions,
acceptance, and stigmas become personally relevant to individuals diagnosed with
mental illness (Granello & Gibbs, 2016; Kroska et al., 2015; Ray & Dollar, 2014).
Cultural conceptions and stigmas become relevant because individuals subject
themselves to views and beliefs of their culture and stigmas in order to avoid rejection or
becoming an outsider. Cohen and Scheff (1996) argued that through the process of being
labeled mentally ill, individuals may begin to conform to the cultural expectations of that
label. Individuals who are mentally ill may come to anticipate negative societal reactions

to their illness, and consequently, many individuals may refuse to seek treatment in order
to avoid the stigma of being labeled mentally ill (Link & Phelan, 2013; Markowitz et al.,
2011; Szeto et al., 2013; Thoits, 2011).
In order for individuals to internalize labels associated with mental illness, there
must be meaningful interactions between the receiver of label and the individuals
labeling them (Brohan, Slade, Clement, & Thornicroft, 2010; Granello & Gibbs, 2016;
Kroska et al., 2015; Link & Phelan, 2013; Ray & Dollar, 2014; Thoits, 2011). In Scheff’s
theory, labeling is significantly influenced by social characteristics of the labeler, the
individual being labeled, and the social interactions between the labeler individual
(Granello & Gibbs, 2016; Kroska et al., 2015; Link & Phelan, 2013; Markowitz et al.,
2011). For example, the terms mentally ill and people with mental illness have been used
interchangeably, but the terms can have different connotations for individuals. Granello
and Gibbs (2016) sought to determine whether there were significant differences in
people’s tolerance toward individuals diagnosed with mental illness based on the use of
specific language and labels. The researchers conducted an experimental study
measuring the attitudes of people towards the two terms (Granello & Gibbs, 2016).
Findings revealed that those who encountered the term the mentally ill were more likely
than those who encountered the person-first language (people with mental illness) to have
images of danger or violence associated with individuals labeled mentally ill (Granello &
Gibbs, 2016). Findings from another study revealed that people who encountered the
term mentally ill were less likely to have benevolent or supportive attitudes toward
people with mental illness (Ray & Dollar, 2014). However, limitations of the study

completed by Ray and Dollar (2014) included a smaller sample size, limiting
generalizability of results. Findings from Granello and Gibbs’s study further coincide
with the modified labeling theory in that people tend to negatively label and reject those
who deviate from standard norms in society. Results from Granello and Gibbs’s study
indicate that labels do have a significant effect on tolerance toward people diagnosed
with mental illness.
Impact of Labeling on the Individual
Principles of the modified labeling theory posit that stigmas and labels associated
with having a mental disorder can cause individuals to withdraw from society, impact
their emotional response to mental illness, conceal their diagnosis, or refuse to educate
others about mental illness (Dolphin & Hennessey, 2017; Link & Phelan, 2013; Link et
al, 1989; Markowitz et al., 2011; Ray & Dollar, 2014). Results from other studies have
revealed that being labeled with a diagnosis of mental illness can have a negative impact
on individuals’ socioeconomic, educational, and psychological well-being (Breslau,
Lane, Samson & Kessler, 2008; Cruwys & Gunaseelan, 2016; Szeto et al., 2013;
Wynaden et al., 2014).
Premises of the theory further implied that individuals diagnosed with mental
illness may develop expectations that others will reject or devalue them due to their
mental illness (Granello & Gibbs, 2016; Moses, 2009; Kroska et al., 2015; Perry, 2011).
Kroska et al. (2015) supported the premise that having a psychiatric label resulted in
individuals being vulnerable to criticisms and rejections of their abilities, skills, and
competence from others. Participants included 180 undergraduate students who had

similar educational backgrounds (Kroska et al., 2015). Results also revealed that men
rejected suggestions from any teammate who had a previous history of mental illness
more than they rejected suggestions from other teammates (Kroska et al., 2015). In
contrast, for women, the psychiatric status of their teammates did not influence their
desire to consider their suggestions (Kroska et al., 2015). In addition, students educated
on the issue of stigma in mental health had reduced resistance to influence from
teammates who had no previous history of mental illnesses (Kroska et al., 2015).
Findings from this study supported the premise that the use of psychiatric labels to
describe individuals with mental illness leads to rejection from others.
Results from other studies have revealed that after individuals have been
diagnosed with a mental illness, the label of being mentally ill can have a negative
impact on their socioeconomic well-being, their educational outcomes, and their
psychological well-being (Breslau, Lane, Samson & Kessler, 2008; Cruwys &
Gunaseelan, 2016; Szeto, Luong, & Dobson, 2013; Wynaden et al., 2014). The diagnosis
of a mental disorder can adversely affect a persons’ ability to secure employment due to
the employers’ perceptions that there may be productivity loss resulting from
absenteeism or poor quality of work (Luong, & Dobson, 2013). Thornicroft et al. (2016)
found that when it came to the topic of disclosing mental illness to employers,
participants stated that they would not inform their employers for fear of being
discriminated against. For individuals diagnosed with mental illness this reluctance and
fear in disclosure can further lead to a loss of income, unemployment, and a limitation in
employment opportunities (Thornicroft et al., 2016). The diagnosis of mental health

problems results in an enormous financial burden that affects a persons’ social and
psychological well-being. Also, the diagnosis of a mental disorder can adversely affect a
persons’ ability to secure employment due to productivity loss, resulting from
absenteeism or poor quality of work (Luong, & Dobson, 2013). In addition, a lack of
financial resources related to living in poverty may exacerbate issues related to labeling
for the mentally ill because poverty hampers the person’s ability to ability to obtain
treatment for mental illness (Ray & Dollar, 2014; Szeto, Luong, & Dobson, 2013).
Individuals who are poor have less resources available to dedicate to improvements in
their mental health status; the added effects of mental health stigmas have been linked to
the ease of their internalization of mental health labels
(Ray & Dollar, 2014).
Furthermore, labels and stigmas against mental illness may have a strong and
enduring effect on an individuals’ psychological well-being (Hatzenbuehler, Phelan, &
Link, 2013; Kendra, Mohr, & Pollard, 2014; Van der Sanden, Bos, Stutterheim, Pryor, &
Kok, 2013). The stigmas against mental health have been associated with negative
psychological outcomes such as lower self-esteem, irritability, depression, feeling
misunderstood, feelings of indignity, and feelings of shame (Chronister, Chou & Liao,
2013; Drapalski et al., 2013; Kendra et al., 2014; Link & Phelan, 2014; Van der Sander
et al., 2013; Zellmann, et al., 2014).
Cruwys and Gunaseelan (2015) applied premises of modified labeling theory in a
study that assessed the connections between a mental health label with self-worth and
sense of well-being. Participants consisted of 250 people diagnosed with depression. The

researchers found that the experiences of being stigmatized with mental illness stigmas
was associated with poorer overall well-being. The variable of well-being was assessed
in the areas of depression, anxiety, stress, and life satisfaction. The Cruwys and
Gunaseelan (2015) study was one of the first studies to demonstrate that social
identification as being mentally ill is associated with the experience of discrimination and
poor well-being. The results which showed that mentally ill individuals expected
discrimination and reported lower well-being supported the premises of modified
labeling theory. Modified labeling theory predicts that those with a mental health label,
whether the label has already been applied to an individual or an individual is expecting a
label are more likely to experience stigma as a powerful pressuring source in their lives
and might possess a more negative self-concept about themselves. The label and the
stigma that ensues make these individuals more vulnerable and more susceptible to
discrimination (real or expected) and to lower societal involvement.
Premises of the modified labeling theory further suggests that the factor which
links labeling to psychological distress is the personal, internalization of the negative
attitudes and stereotypes about the stigmatized condition (Mustillo et al., 2013). The
process of being labeled mentally ill has been linked to individual tendencies to link to
internalize the labels, such as being incompetent and dangerous and to create a lasting
impression on one’s identity (Markowitz, et al., 2011; Mustillo, Budd, & Hendrix, 2013).
For instance, Mustillo, Budd, and Hendrix (2013) used principles of modified labeling
theory to examine the psychological distress among White girls who had been labeled
obese by parents and friends. Results from this study indicated harmful and long-term

effects of labeling when the label was internalized at a young age. The study found that
labeling had both proximal and distal effects for young girls. Results showed that the
proximal affects that showed up in the girls immediately after being labeled included
feelings of sadness, discontent with self, lowered self-image. The distal effects included
lower self-image long after labeling and increased self-consciousness. Mustillo et al.
(2013) also found that weight-based stigmas and labeling had varying effects on the girls
over their life course depending on when the individual experienced the labeling.
In another study, Markowitz et al. (2011) utilized principles of modified labeling
theory to examine 129 mothers’ perceptions of their children with schizophrenia and the
stigmas attached to those perceptions. Findings from the study revealed a circular
interaction between the mothers’ perceptions of their children and outcomes for the
children. Results showed that the mothers’ appraisals of their children’s mental health
affected the children’s perceptions about their own conditions, which ultimately affected
the clinical outcomes for the children. The clinical outcomes ultimately affected the
mothers’ perceptions of their children’s mental health. Markowitz et al. (2011)
effectively used premises of modified labeling theory as a framework for explaining the
relationship between mental health stigmas and their subsequent effect on outcomes for
individuals with mental illness. This further implied the use of the selected theory
(modified labeling theory) for this present research study. As reported above, the
modified labeling theory implied that labels do impact individuals diagnosed with mental
illness negatively and can have profound negative effects (i.e., rejection, social
withdrawal, lack of mental health treatment) for the mentally ill. Research questions

identified for the present study further built upon the modified labeling theory as it
relates to one’s view of those diagnosed with mental illness and its impact on help-
seeking behavior.
Mental Health Defined
According to the 5th edition of the Diagnostic Statistical Manual, a mental
disorder is a clinically significant disturbance cognition, emotion regulation, or behavior
that indicates a dysfunction in mental functioning (Alang, 2015; Sickel et al., 2014).
Mental illness is a condition that impacts a person's thinking, feelings, or mood (Kessler
et al., 2010; Nordberg et al., 2013). Mental illness may also affect a person’s ability to
relate to others, and it may affect a person’s ability to function on a daily basis (National
Institute of Mental Health [NAMI], 2015; Sickel et al., 2014).
Prevalence of Mental Illness
Mental illness is a health condition that affects approximately 400 million people
worldwide (Sosulski, & Woodward, 2013; Turner, Wildschut, Sedikides, & Gheorghiu,
2013). Mental illness is a public health concern that affects almost every person living in
the United States either directly or indirectly (Aguiniga, Madden, & Zellmann, 2016;
Johnson & Riles, 2016). According to the National Institute of Mental Health, in any
given year, 1 in 5 adults in the U.S. suffer from a diagnosable mental disorder
(Baumeister, Hawkings, Lee Pow, & Cohen, 2012). In addition, serious mental illnesses
affect approximately 15 to 21 million Americans (Salzer, 2012).
Researchers have estimated that 27% of people between the ages of 18 and 24
years have a diagnosable mental illness (Johnson & Riles, 2016). Several researchers

have indicated that approximately 1.8 million college students seek help for mental
illness from university counseling centers each year (Hayes et al., 2011; Johnson & Riles,
2016). These numbers indicate that about a third of college students have a diagnosable
mental illness, and this population is especially vulnerable to the stressors of college life,
which could exacerbate the symptoms of mental illness (National Alliance on Mental
Health, n.d.).
Stigma of Mental Health
The stigma of mental illness is one of the most pronounced obstacles to progress
in improving mental health (Abdullah & Brown, 2011; Cheng et al., 2013). Stigmas
about mental illness result in people using degrading attitudes and negative labels toward
individuals diagnosed with mental illness (Arboleda-Flórez, & Stuart, 2012; Butler,
2014). Negative depictions of those diagnosed with mental illness can be widely found in
advertisements, films, and other media outlets (Aguiniga, Madden, & Zellmann, 2016;
Kendra, Mohr, & Pollard, 2014; Talbott, 2013; Yiyi, Lu, & Bijie Biel, 2017).
Stuart and Arboleda (2012) looked at the issue of mental health stigma from a
public health perspective and how stigmas can translate into internalized stigma. The
article provided a partial meta-review of other studies which discussed mental health
stigma and provided a deep insight into the concept of mental health stigma. The authors
stipulated that mental health stigma is a serious concern among mental health
practitioners. Results from other studies showed that individuals diagnosed with mental
illness frequently find themselves in a variety of troublesome situations once their stigma
becomes internalized, such as the inability to obtain employment. In turn, those

experiencing an inability to obtain employment due to the stigma of mental health have
reported being treated different or viewed as being weak. This stigma further leads
unemployed individuals diagnosed with mental health illnesses to not use mental health
services and therefore, not benefit from available mental health treatment (Staiger,
Waldmann, Rusch, & Krumm (2017).
Wright, Jorm, and Mackinnon (2011) conducted a survey-based quantitative
study to address the relationship between the types of labels that are applied to mental
health disorders (and their severity) and subsequent perceptions of mental health stigma.
The authors used a phone survey of 3,726 young adults (ages 12 to 25) in Australia and
collected their demographics, along with information about their views on mental health
issues. The researchers also presented participants with several vignettes of various
mental health severity. The authors found that the way various mental health conditions
were labeled, along with the specific words indicating severity of these mental health
conditions correlated positively with the way the participants exhibited their mental
health perceptions (i.e., seeing someone with mental illness as being sick), prejudices,
and stigma. Findings indicated that accurate psychiatric labels by young people may
assist young people in reducing perceptions of weakness in individuals diagnosed with
mental illness (Wright, Jorm & Mackinnon, 2011). The article is helpful as it illuminates
another aspect of mental health stigma and the external presentation of mental health
conditions. Stigmas are also related to negative beliefs (e.g., people with mental health
problems are dangerous), prejudicial attitudes (e.g., desire to avoid interaction), and

discriminatory practices (e.g., failure to hire or rent property to such people) that are
directed toward a particular group of individuals (Clark et al., 2013; Corrigan, Druss, &
Perlick, 2014; Nordberg, 2013; Zellmann, Madden, & Aguiniga, 2014).
Types of Stigmas
The stigma associated with having a mental illness can manifest itself in different
types of stigmas, which are public, self, and perceived. Public stigma refers to the
perception that a person who seeks psychological treatment is undesirable or socially
unacceptable (Charles, 2013; Parcesepe & Cabassa, 2013; Pedersen & Paves, 2014;
Topkaya, 2014). This type of stigma pertains to the negative attitudes and behaviors of
society toward people with mental illness (Charles, 2013; Kranke et al., 2012; Lien et al.,
2015; Topkaya, 2014). Furthermore, public stigma focuses on the negative conceptions
about mental illness, which can lead to prejudice against individuals with mental health
disorders (Charles, 2013; Lien et al., 2015; Parcesepe & Cabassa, 2013; Pedersen &
Paves, 2014). Public stigma refers to the prejudice and discrimination endorsed by the
general population that affects a person (Corrigon et al., 2012; Gaddis, Ramirez, &
Hernandez, 2018). Research has shown that when people find out that a person has been
diagnosed with a mental health illness, they tend to limit their connections with that
person. This limiting of connections is a direct manifestation of the consequence
associated with public stigma. In turn, the reduced connections with people diagnosed
with mental illness or seeking treatment demonstrates how such individuals are socially
rejected beings (Charles, 2013; Parcesepe & Cabassa, 2013).

With self-stigma, individuals apply negative beliefs and attitudes associated with
mental disorders to themselves (Charles, 2013; Lamin et al., 2016; Topkaya, 2014). For
example, Topkaya (2014) conducted a correlational study of 362 college students
assessing the relationships between gender, self-stigma, and public stigmas on
psychological help seeking among three college students using various surveys. A
hierarchical regression analysis and a t-test were utilized in the data analysis procedure.
Results demonstrated that although both gender and self-stigmas significantly predicted
attitudes toward seeking psychological help, public stigma was not a significant predictor
of attitudes toward seeking psychological help (Topkaya, 2014). Results further indicated
that males were more likely to experience self-stigma and public stigma in comparison to
females. One limitation of this study was that the study did not include of a variety of age
groups as it was limited to only university students. The relevance of this study
illustrated how gender was associated with seeking mental health treatment whereby
males experienced self-stigma, and they therefore tended not to seek mental health
treatment in comparison to women.
Data from past research has revealed that individuals who experience self-stigma
tend to experience anger and resort to concealment, which may keep them from seeking
treatment (Kranke et al., 2012; Lamin et al., 2016; Lannin, Vogel, Brenner, Abraham, &
Heath, 2016). Lamin et al. (2016) examined whether self-stigma negatively impacted
decisions to seek information about counseling and mental health concerns for university
students. Data were collected through the use of various surveys. Findings for this
quantitative study demonstrated that individuals in need of mental health treatment were

reluctant to access mental health treatment information if they experienced high levels of
self-stigma (Lamin et al., 2016). Limitations for this study included the ethnicity of
participants as the majority of the sample was European American.
In considering implications of self-stigma across other cultures, Boyd, Adler,
Otilingam, and Peters (2014) conducted a quantitative review of the Internalized Stigma
of Mental Illness (ISMI) scale in order to assess its findings across multiple cultures. The
authors searched for studies that used the instrument in a variety of languages and
analyzed the validity of the instruments. They found that self-stigma was often correlated
positively with depression, higher severity of symptoms, and lower self-esteem. This
study provided a unique contribution to this project as it highlights the multinational
aspect of mental health stigma.
Perceived stigma has been conceptualized as assessing participants’ beliefs about
other people’s attitudes toward people with a mental illness (Lien et al., 2015). Perceived
stigma is also the perception that people in one’s social group will view someone who
seeks treatment as less socially acceptable (Jennings et al., 2015; Lien et al., 2015). Lien
et al. (2015) examined the relationships between perceived public stigma toward mental
illness and psychosis like experiences. The researchers assessed how perceived stigma,
self-stigma, and self-reliance were related to treatment-seeking among 246 college
students. Results from the study revealed that higher levels of perceived stigma and
selfstigma were negatively related to attitude towards treatment-seeking. The Lien et al.
(2015) study is relevant to my research because findings indicated that perceived stigma
influenced whether students sought treatment for mental health illnesses.

Effects of Stigmas Against Mental Health on Individuals
Stigmas against mental illness can lead to harmful effects for individuals
(Charles, 2013; Clark et al., 2013; Corrigan et al., 2014; Ilic et al., 2013; Link & Phelan,
2014; Sickel et al., 2014). Harmful effects of mental illness stigma include discrimination
of the individual diagnosed with a mental disorder, paternalistic treatment, and avoidance
(Ilic et al., 2013). Researchers developed a multifaceted Stigma Scale to assess
dimensions (hostile discrimination, benevolent discrimination, taboo, and denial) of
stigma experienced in interpersonal interactions with others (Ilic et al., 2013). This scale
defines benevolent discrimination as an intentioned special-care treatment, taboo as a
lack of conversation about the illness, and denial as a lack of acceptance of the illness
with the associated allegation that the illness was only invented (Ilic et al., 2013). Using a
total of 367 participants, the researchers conducted a mixed methods study to explore the
consequences associated with the personal experience of being stigmatized. Findings
from the study completed by Illic et al. (2013) revealed that individuals who reported any
of the four types of stigmas reported the experience as a stressor that impaired their
recovery from mental disorders.
Individuals with mental illness are frequently subjected to discriminatory
behavior from others and can experience discrimination in all aspects of their lives.
Individuals diagnosed with mental illness encounter discrimination and stigma in the
workplace, when it comes to applying for housing and with legal issues. For example,
studies have shown that employers, based on their perception of mental health illness, are
less likely to hire persons who are labeled mentally ill (Brown et. al, 2010; Khumalo,

Temane, & Wissing, 2012; Sickel et al., 2014). This further validates the notion that
individuals diagnosed with mental illness fear disclosing their illness to employers. In
addition, landlords were less likely to lease apartments to individuals who are diagnosed
with mental illness due to perceptions of mental illness (Aubrey et al., 2015). Findings
from studies have shown that police are more likely to falsely press charges against
individuals with mental illness for violent crimes (Brown et al., 2010; Corrigan et al.,
2014; Illic, 2013; Sickel et al., 2014).
Quinn, Williams, and Weisz (2015) completed a study of 105 adults with mental
illness who reported their experiences of discrimination, anticipated discrimination, and
social devaluation. Results from a correlational analysis showed a positive relationship
between discrimination and anticipated discrimination. The data revealed that the more
individuals experienced discrimination due to their mental illness, the more they
anticipated discrimination in the future. Findings also showed that social devaluation
(anticipated social stigma) from others was also related to greater internalized stigma for
participants. This study had a relatively small sample size, which limited the
generalizability of the results. However, findings from the study are relevant to my
research as the findings illustrated the impact of mental illness stigma on anticipated
discrimination and social devaluation.
Chronister, Chou, and Liao (2013) examined 101 patients to determine the effects
of mental health stigmas. The researchers further assessed how individuals who
internalize stigmas impact their recovery and quality of life during and after treatment.

Results showed that internalized stigmas were negatively associated with patients’
recovery and quality of life. Results also indicated that individuals diagnosed with mental
illness who concealed their history of mental illness from friends, family, etc., to avoid
rejection or withdraw from social interactions, internalized stigmas to a greater extent
than those who did not conceal their illness (Chronister et al., 2013). As a result,
individuals who internalized stigmas experienced poorer mental health recovery than
those who did not internalize the stigmas. The study employed a large sample, which
enhanced generalizability and trustworthiness of the results. However, the study could
have been improved by including patients from different stages of mental health
disorders (such as light to severe).
Drapalzki et al. (2013) also found that internalized stigmas have a negative
impact on an individual’s self-concept, social relationships, psychiatric health, and well-
being in the recovery process. Drapalzki et al. (2013) assessed the prevalence of
internalized stigma among one hundred individuals diagnosed with a serious mental
disorder to assess the relationship between internalized stigma, self-concept, and
psychotic symptoms. Results indicated that internalized stigma was associated with
lower self-esteem, low self-efficacy, and greater psychiatric distress. Findings from both
studies Chronister et al. (2013) and Drapalzki et al. (2013) are relevant to my research
because results revealed how the internalization of stigmas affected the patients’
subsequent recovery and quality of life.

Stigmas as Barriers to Help Seeking for Mental Illness
There is growing evidence that stigmas against mental health affects treatment
utilization, including treatment engagement, compliance, interpersonal relationships,
perceptions of care, and treatment effectiveness (Quinn, Williams, & Weisz, 2015;
Tucker et al., 2013). For instance, Clement et al. (2014) conducted a meta-analysis of
144 research studies (which included nearly 100,000 participants) in order to examine the
relationship between mental health stigma and help seeking. The researchers found a
small negative average correlation between stigma and seeking help (d = -0.27); the
negative correlation suggested that the individuals with strong stigmas around mental
health conditions were less likely ones to seek help for mental illness.
Mental health stigma can have an impact, not only on individuals diagnosed with
a mental disorder but among mental health treatment providers as well. A mental health
providers’ perception of those diagnosed with mental illness can have important
implications for serving this population and reducing stigma related behaviors that may
impact their clients’ outcomes. For instance, Stromwall, Holley, and Kondrat (2012)
completed a quantitative research study assessing 51 peer employees and 52 licensed
clinicians view on the extent of mental health stigma and discrimination. Results
indicated that clinicians, women, and those who had observed a friend with a mental
illness treated unfairly perceived significantly higher levels of public discrimination than
their counterparts (Stromwell, Holley, & Kondrat, 2012). Clinicians perceived more
discrimination than their peer employees, and men’s perceptions of discrimination of

those diagnosed with mental illness were more strongly affected by personal contact
(Stromwell, Holley, & Kondrat, 2012).
The stigma of mental illness exists, not only in the US, but in all cultures and
remains a strong barrier to individuals seeking psychological services worldwide
(Arboleda-Flórez, & Stuart, 2012; Covarrubias, & Han, 2011; Vogel et al., 2017).
Several researchers have shown that the stigmas associated with mental illness keeps
individuals diagnosed with a mental disorder from seeking professional treatment
(Arboleda-Flórez & Stuart, 2012; Cheng et al., 2013; Corrigan, Druss, & Perlick, 2014;
Fripp & Carlson, 2017; Masudo et al., 2012; Mendoza, Masuda, & Swartout, 2015). For
instance, Cheng et al. (2013) conducted a quantitative study to assess the effects of
psychological distress and psycho-cultural variables on perceived stigmatization by
others and self-stigma of seeking help psychological help distress (Cheng et al., 2013).
The sample consisted of 609 African American, Asian, and Latino college students from
a large Midwestern public university. The researchers used several surveys to collect data
on the variables of interest. Results from this study showed that across all three racial
groups, higher levels of psychological distress and perceived racial/ethnic discrimination
predicted higher levels of perceived stigmatization against individuals for seeking help
for psychological distress, which in turn prevented individuals with a mental illness from
seeking help. In another study, Mendoza et al. (2015) examined whether mental health
stigma and selfconcealment impacted attitudes towards seeking professional treatment
for mental illness. The quantitative, cross-sectional study consisted of 129
undergraduates (mostly female) in the state of Georgia. Results indicated that mental

health stigma was uniquely associated with overall help-seeking attitudes, recognition of
need for psychotherapeutic help, stigma tolerance, and interpersonal openness (Mendoza
et al., 2015). A limitation of this study included the race of the participants, which
limited the generalizability of results from the study. Findings from this study implied
that there was a significant negative association between mental health stigma and
recognition of need of psychiatric services.
In another quantitative study, Fripp and Carlson (2017) assessed how mental
health stigmas impacted treatment seeking for individuals with mental illness.
Participants consisted of 129 African American and Latino community participants.
Results from a linear regression analysis revealed that attitude toward help seeking was
inversely correlated with strong stigmas toward mental illness among African American
and Latino individuals. Limitations of the study included exclusion of many other racial
and ethnic groups (i.e., Asian Americans), which limited the generalizability of results to
a larger population (Fripp & Carlson, 2017). Findings from Fripp and Carlson’s research
(2017) were relevant to my study because the results revealed that the stigma of mental
health illness was a factor that inhibited seeking mental health treatment.
Vogel et al. (2017) assessed the relationship between two types of stigmas (i.e.,
public and self-stigma) and attitudes toward seeking psychological services for 3,276
international students. Results indicated that stigma impacted the attitudes toward
seeking psychological help among students from 10 countries and regions (Australia,
Brazil, Canada, Hong Kong, Portugal, Romania, Taiwan, Turkey, the UAE, and the
U.S.). In another study, researchers linked two international data sets to assess the

relationships between public stigma and self-stigma among 1,835 participants in 14
European countries (Evans-Lacko et al., 2012). This study employed a quantitative,
survey research design utilizing a linear regression analysis. Results indicated that higher
rates of help seeking were found in countries where there were fewer stigmatizing
attitudes about mental illness. Findings from the study suggested that public attitudes and
behavior were associated with how individuals with mental illness perceived their illness,
their helpseeking behavior, and their utilization of treatment (Evans-Lacko et al., 2012).
Pedersen and Paves (2014) assessed whether perceived public stigma and
personal stigma served as barriers to mental health treatment seeking for young adults. A
sample of 386 college students completed surveys assessing mental health symptoms,
treatment experience and attitudes, perceived public, and self-stigma. Results indicated
that participants experienced higher levels of perceived public stigma than personal
stigma. Negative attitudes toward treatment were related to perceived public stigma and
negative attitudes toward treatment were related to personal stigma (Pedersen & Paves,
2014). In other words, attitudes towards treatment and perceived public stigma were
negatively correlated; the more stigma a person felt, the less likely s/he were to consider
engaging in mental health treatment. Limitations for this study included that this study
was limited to Caucasian and Asian Americans. Participants also primarily came from
first and second-year students at one university setting, which limited the generalizability
of the findings. Results from this study illustrated how perceived stigma and public
stigma affected treatment seeking for individuals diagnosed with mental illness.

Researchers also used quantitative research designs to investigate the predictive
relationships between perceived public stigma, group identification, perceived legitimacy
of discrimination, and avoidant behaviors in relation to mental health treatment (i.e.,
secrecy and social withdrawal) (Schibalski et al., 2017). This survey research consisted
of a sample of 9,829 individuals from Zurich, Switzerland. Data were analyzed using a
correlational analysis. Results indicated that the perceived public stigma was positively
correlated with avoidant stigma coping. Stigma stress and shame were also positively
related to avoidant stigma coping. In other words, participants were less likely to engage
in treatment for their mental health concerns when they expected others to label them.
Limitations for this study included the limited generalizability of results due to the fairly
homogenous sample of young to middle-aged adults who were mostly females
(Schibalski et al., 2017).
Corrigan et al. (2014) reviewed the impact of mental illness stigma on help
seeking for mental health issues and participating in mental health care. Corrigan et al.
(2014) completed a meta-analysis literature review of 72 articles assessing the effects of
anti-stigma approaches with individuals diagnosed with mental illness. Results indicated
that the effect of stigma is influenced by the knowledge of mental illness and that this is
central to reducing its negative impact on help seeking (Corrigan et al., 2014). The
impact of mental illness can range from a reluctance to seeking mental health treatment
to not wanting others to know about the mental illness (Butler, 2014; Corrigan, et al.,
2014;

Sickel et al., 2014; Zellmann, Madden, & Aguiniga, 2014). In addition, decreased
compliance of treatment, increased mental health systems, and reduced coping effects
have been associated with mental health stigma (Sickel et al., 2014).
Past research has shown that self-reliance is a barrier that prevents individuals
with mental health conditions from seeking help (Brown et al., 2015; Jennings et al.,
2015). The stigma of self-reliance is the idea that one does not need professional mental
health services to deal with a mental health issue (Brown, Rice, Rickwood, & Parker,
2015). Brown et al. (2015) found that self-reliance, which specifically manifests itself in
Americans, can also be a negative result of one experiencing stigma and considered to be
a treatment seeking barrier. Brown et al. (2015) conducted a meta-analysis of 62
quantitative and qualitative published studies related to barriers to seeking care for
mental health symptoms for at risk young people. The results indicated that individuals
who were raised in cultures more focused on individuality, such as in the United States,
tended to ascribe more importance to dealing with their mental health concerns
themselves, which relates back to the specific definition of self-reliance (Brown et al.,
2015).
Kendra, Mohr, and Pollard (2014) examined whether the stigma of having
psychological problems was a barrier to individuals seeking mental health treatment as
well as how stigmas against mental illness influenced the experiences of those involved
in mental health treatment. Researchers explored whether stigmas (self-stigma and
perceived public stigma) impacted levels of individual depression, the working alliance,
and therapeutic engagement in treatment. The exploratory study consisted of 42

counseling center students from a university in the US. Results indicated that self-stigma
was positively associated with initial depression, negatively associated with initial
working alliance, and unrelated to initial engagement. Findings further indicated that
perceived public stigma decreased over the first few psychotherapy sessions, but
selfstigma remained constant for participants. Results from the study indicated the impact
that stigma had on the outcomes of mental health treatment. Results from the study
indicated that stigma against mental illness can adversely impact those seeking mental
health treatment and those involved in psychiatric treatment (Kendra et al., 2014).
College Students and Mental Health
Mental illness among college students represents a significant public health issue
in the United States (Arboleda-Flórez, & Stuart, 2012; McIntyre, Rowland, Choi, &
Sarkin, 2014; Nam, 2013; Nordberg et al., 2013; Salzer, 2012; Schoen & McKelley,
2012). According to the latest data by the American Psychological Association (2017),
nearly 25% of college students in the United States take psychotropic medications of one
kind or another, and this number potentially indicates the pervasiveness of mental illness
among the college student population (APA, 2017). Research by Kirsch, Doerfler, and
Truong (2014) revealed that 45% of college students experienced some type of
psychological disorder during their college careers. Results from several studies have
shown that almost 50% of college-age individuals have been diagnosed with a mental
illness (Hardy, Weatherford, Locke, DePalma, & D'Iuso, 2011; Hayes, Weatherford,

Locke, DePalma, & D’Iuso, 2011; Hayes et al., 2011; Kranke et al., 2013). In addition,
researchers have posed concerns about the impact of untreated mental illnesses for
college students.
Researchers have found that most mental health disorders first appear by the age
of 24 years in which the last six of those years are typically the time that most individuals
attend college (Jennings et al., & Lee, 2015; Marsh & Wilcoxon, 2015; Pedrelli, Nyer,
Yeung, Zulauf, & Wilens, 2015; Schindler & Kientz, 2013). The transition into college
and the first couple of years as an undergraduate student in college can be tough for
students, and the transition to college could be even more stressful for those who
experience emotional or mental distress (Karatekin, 2017; Knowlden, Hackman, &
Sharma, 2016). Mental health problems can potentially impede an individual’s successful
completion of college (Moore et al., 2017). Statistics show that 86% of students with
mental illnesses withdraw from college prior to completing their degree (Salzer, 2012;
Schoen & McKelley, 2012) compared to a 45% withdrawal rate for the general student
population (Kranke et al., 2013; Salzer, 2012; Schindler & Kientz, 2013; Schoen &
McKelley, 2012).
Eisenberg, Hunt, and Speer (2013) sought to empirically determine the
prevalence of mental health symptoms among college students. The researchers
conducted a quantitative study to conduct brief mental health screening surveys of
14,175 university students. Results revealed positive screenings for the following
categories of mental illness: 17.3% for depression, 15.3% for non-suicidal self-injury,
7.0% for generalized anxiety, 6.3% for suicidal ideation, and 4.1% for panic disorder.

Results from the Eisenberg et al. (2013) study showed that there was a high rate of
mental health problems among college students. In addition, students with past or current
financial stresses had a substantially higher likelihood of depression, anxiety, and
suicidal ideation. Findings from the Eisenberg et al. (2013) study could be used to
emphasize the need for addressing mental health illness among the college student
population and the importance of taking into consideration stressors that may further
impact college students’ well- being. The Eisenberg et al. (2013) study was limited to
undergraduate students only and did not refer to treatment uses typical of graduate or
medical students.
There is a high prevalence of mental health illness among college age students,
and approximately 1.8 million college students seek help from university counseling
centers each year (American College Health Association, 2008; Hayes et al., 2011;
Johnson & Riles, 2016). However, there are several factors that influence college
students’ use of mental health services. For example, Sontag-Padilla et al. (2016)
examined factors that influenced college students’ use of mental health services across 39
college campuses in California. The researchers used a logistic regression to examine the
association between students’ use of mental health service, student characteristics, and
campus environments. Results indicated that students were more likely to seek treatment
on campuses that provided mental health services on site (Sontag-Padilla et al., 2016).
Ketchen Lipson, Gaddis, Heinze, Beck, and Eisenberg (2015) also examined
various characteristics at universities (size of class enrollment, type of degree granting
institution, public versus private institution) impacted student mental health and student

utilization of mental health services. The researchers utilized a quantitative research
design to assess 43,210 undergraduates at 72 campuses in the United States. Results from
the data showed that mental health problems appeared to be highest and treatment
utilization lowest at universities that had fewer resources dedicated to addressing
students’ mental health needs (Ketchen Lipson et al., 2015). The results further revealed
that institutions with doctorate granting institutions, institutions with small enrollments,
and undergraduate colleges tend to have higher treatment utilization. Findings from this
study are relevant to my research because the results demonstrated how certain
characteristics of a college impacted students’ mental health and their utilization of
mental health treatment services.
Mental Health Stigmas in the College Student Population
Several researchers have found differences in students’ attitudes toward mental
illness based on the major program of study (Theriot & Lodato, 2012; Zellman, Madden,
& Aguiniga, 2014). Theriot and Lodato (2012) conducted a quantitative study to
compare attitudes of social work students and general college students’ perceptions of
mental health stigmas and the dangers of mental health diagnoses. The study was based
on a sample of nearly 200 students. Findings indicated that social work students had
more positive attitudes toward mental illness than other students. Social work students
had less fear, were considered to be less avoidant of individuals with mental illness, and
more willing to help individuals with mental illness compared to other university
students (Theriot & Lodato, 2012). The results were relevant to this study because the
results revealed how a student’s educational background (i.e., social work) could affect

their perceptions, prejudices, and attitudes towards mental illness stigma. This study was
also an example of how negative effects of attitudes and perceptions of mental illness
could be overcome with education and awareness of mental illness (Theriot & Lodato,
2012).
Zellman et al. (2014) conducted a quantitative, descriptive, bivariate analysis of
mental health stigmas attitudes among 198 midwestern public university students who
were enrolled in a Bachelor of Social Work program. Results revealed that students who
found the job of social work more rewarding held significantly less bias towards stigma
surrounding clients with mental health problems and were more comfortable discussing
mental health stigma and other issues with patients. The study was based on a large
representative sample of students but only consisted of students enrolled in selected
social work courses that semester; thus, there may be potential bias in the results.
In another study Aggarwal et al. (2013), examined the impact of including
literature regarding mental illness in the curriculum for first year students. The
researchers found that students who were educated on mental illness had a decrease in
their levels of stigmatization against mental illness. Medical students who experienced
the curriculum showed an increased willingness to interact with individuals diagnosed
with a mental illness (Aggarwal et., 2013). Results further indicated that students who
attained more knowledge about mental illness tended to have more favorable attitudes
towards individuals diagnosed with mental illness. In another study, Kosyluk et al.
(2016) examined how being presented information about mental illness affected people’s
stigmas around mental illness in which similar results were obtained. The quantitative

study consisted of 198 college students who were randomly assigned to three conditions
of varied presentations about mental health stigma. The three conditions were either a
contact based anti-stigma presentation, education-based presentation, or a control
condition. Results revealed that students who received contact or education-based
explanations of mental health stigma demonstrated reduced prejudice towards mental
health issues and had more accepting attitudes towards seeking treatment for mental
health issues (potential theirs and of others). Kosyluk et al. (2016) also found that there
was no differences in results for education-based and contact-based conditions. Results
from this study are relevant to my research as the findings indicated that mental health
stigma is a dynamic and changeable concept for college students. Findings further
supported the notion that stigmas against mental health could be reduced with
appropriate interventions.
Other researchers have explored whether exposure and direct contact with
individuals diagnosed with mental illness were related to changes in student’s perception
towards the stigma of mental health (Eisenberg, Downs & Golberstein, 2012; Lyndon,
Crowe, Wuensch, McCammon, & Davis, 2016). For example, Eisenberg et al. (2012)
completed a quasi-experiment to determine how contact with individuals receiving
mental health treatment affected participant’s personal stigmas related to mental health
issues. The sample consisted of 1,605 undergraduate students attending universities in
the United States. Researchers used multivariable regression to estimate the effect of
being assigned to a roommate with a history of mental health treatment affected
participants’ stigmatizing attitudes. Findings indicated that contact with a person who

was seeking mental health treatment was related to an increase in participants’
stigmatized attitudes toward those seeking treatment for mental health issues. However,
participants who had prior exposure to mental health treatment of their own, contact with
an assigned roommate who was utilizing mental health services did not yield any change.
Findings from the Eisenberg et al. (2012) study are relevant to my study as the results
showed that naturalistic contact with mental health users does not inevitably lead to
improved attitudes or reduced stigmas about mental disorders.
In another study, Lyndon et al. (2016) assessed the predictive relationships
between judgments made about people with mental illness based on personal familiarity
with those individuals, perceptions that personality is unchangeable, beliefs about the
causes of mental illness, and the desire for distancing one’s self from individuals with
mental illness. This quantitative study consisted of 159 undergraduate psychology
students. Data analysis was completed through the use of a multiple regression analyses.
Findings indicated that familiarity with people with a mental illness predicted less desire
for social distance (Lyndon et al., 2016). Results illustrated that students who felt that
personality traits were unchangeable were more likely to stigmatize individuals with
mental illness. Findings from this study showed how judgements, beliefs, etc., influenced
stigma associated with mental illness in university students.
Some college students with mental illness may fear their relationships with their
on-campus peers may be impacted once their peers find out that they have a mental
illness (Salzer, 2012; Theriot & Lodato, 2012; Venille, Street, & Fossey, 2014). For
instance, Salzer (2012) quantitatively examined the types of campus experiences (such as

social interactions, involvement in extracurricular activities, etc.) of college students with
mental illnesses compared to the general student body. Data were collected using the
College Students Experiences Questionnaire (CESQ), which assesses student campus
experiences and engagement, relationships with others on the campus, and the degree to
which students were satisfied with their experiences at a particular institution. Results
revealed that college students with mental illnesses reported poorer relationships with
others than students without mental illness. Results further showed that less engagement
was associated with lower graduation rates for students with mental health concerns
(Salzer, 2012). Students with mental illness also reported they were treated differently by
their peers most of the time because of a mental illness. In another study Venille, Street,
and Fossey (2014) assessed university students’ preference to disclose or not to disclose
their mental illness to others. Eligible students who reported a diagnosed mental disorder
reported that they preferred not to disclose their mental illness due to fear it would
negatively impact their capacity to obtain employment. Participants reported that
disclosure within their educational program was perceived to carry risks such as stigma,
prejudice, and rejection. More than half of the 20 students who participated in the study
reported that they did not make contact with campus mental health services due to
previous negative experiences associated with prior disclosure of their mental illness
with others (Venille, Street & Fossey, 2014).
Help-Seeking Behavior for College Students Diagnosed with Mental Illness
According to Marsh and Wilcoxon (2015), despite the benefits of seeking professional
mental health services, only about 10% of psychologically distressed college students

seek professional help. Assessing the help-seeking behavior in college students is an
important step toward understanding challenges faced by this population. Lally et al.
(2013) conducted a study which assessed 735 university students’ level of personal and
perceived public stigmas to determine the associations between stigma and help seeking
intention for this population. Results indicated that personal stigma was significantly
associated with a decreased likelihood of help seeking intentions for mental illness
among college students. Researchers reported that being younger than 25 years of age,
having no history of or treatment for mental illness, and having no personal contact with
someone with a history of mental illness were associated with higher levels of personal
stigma (Lally et al., 2013). Perceived stigma was not a predictor of non-help seeking
intention for participants in the study. Limitations of the study included the use of an
adaption of the Discrimination Devaluation scale that had not been previously validated
(Lally et al., 2013). The findings from the Lally et al. (2013) study are relevant to my
research because the findings revealed how stigma may be a barrier to utilization of
mental health services for college students.
Kranke (2013) found that some students with mental health conditions did not
seek treatment due to the lack of awareness of university mental health services. Kranke
(2013) analyzed data from structured interviews of 17 college students who were
diagnosed with a mental health disorder. The goal of the study was to understand these
students’ perceptions of mental health services on campus and their utilization of those
services. The researcher found that while participants generally thought that mental
health services were beneficial to their treatment and eradication of symptoms, most

students did not know the extent of mental health services that their college counseling
centers offered (Kranke, 2013).
In another study, Schwartz, Nissel, Eisenberg, Kay, and Brown (2012) assessed
the utilization of on campus treatment options after a university implemented assertive
outreach, educational and advocacy programs. This predominantly, traditional, orthodox
institution wanted to increase awareness of services and referrals to counseling services
for the undergraduate student body. Students at the university came in for counseling
services, but those seeking treatment tended to have more negative opinions about mental
illness than most college students. Limitations of the Schhwatz study included limited
generalizability of the results to other institutions or student populations since this was a
small, orthodox Jewish urban university. Findings from the study by Schwartz et al.
(2012) revealed that on campus campaigns used to promote awareness of mental illness
could have a positive impact utilization of treatment services.
D’Amico, Mechling, Kemppainen, Ahern, and Lee (2016) sought to determine
what variables prohibited university students from seeking counseling center services.
Variables assessed in the study included the young adults’ mental health literacy, their
perceived stigmas of depression and treatment, their knowledge of treatment benefits and
risks of treatment, their beliefs about alternative therapies, the influence of their social
network, and their use of university counseling services. The cross-sectional,
correlational study consisted of a sample of 107 undergraduate students in the United
States. Findings revealed that college students were less likely to seek counseling
services for depression when they perceived stigma or experienced discrimination from

family and friends. Results also revealed that students who would use alternative forms
of therapy such as yoga, exercise, etc. would be more likely to seek university counseling
services for depression (D’Amic et al., 2016). Limitations of this study included the
smaller sample size (n =107) of students. Results indicated that most participants
generally accepted individuals with mental illness as the majority of participants
indicated that society should treat people with mental illness in a tolerant way. However,
participants further reported that it was difficult to communicate with people with mental
illness. Participants further agreed that everyone had a chance of developing a mental
illness. Findings from this study indicated that students could have favorable attitudes
towards people suffering from mental illness.
Mental Illness in the African American Community Findings from
several studies have revealed that African Americans are disproportionately diagnosed
with psychotic disorders compared to most other racial groups (Schwartz &
Blankenship, 2014; Vinson, Abdullah, & Brown, 2016). African Americans make up
only 12% of the population (40.1 million) of the United States, yet they make up 14.5
to 18.7% (7.5 million) of those affected by mental illness, depending on the source
(Vinson, et al., 2016; Ward et al., 2013). Table 1 showed statistics from a National
Institute of Mental Health (2017) report completed by Substance Abuse and Mental
Health Administration on the reported rates of mental illness for 2016 according to
race/ethnicity. Table 1 also shows the prevalence of psychotic symptoms by
race/ethnicity. The data reveal that African Americans had the highest rate of psychotic
symptoms even though they had the third highest rates of reported mental illness.

Table 1
Prevalence of Mental Illness and Psychotic Symptoms by Race/Ethnicity
Race/Ethnicity National Institute of
Mental Health (2017)
Prevalence of psychotic
Symptoms per Cohen &
Marino (2013)
Mixed Race 26.5%
American Indian/Alaskan
Native
22.8%
Caucasian/White 19.9% 9%
Native Hawaiians 16.7%
African American/Black were 14.5% 15%
Asian Americans 12.1% 9%
Hispanic 15.7% 13%
According to the United States Health and Human Services Office of Minority
Health (2016), African Americans are about 20% more likely than other ethnic groups in
the US to suffer from a mental health disorder. Schwartz and Blankenship (2014)
conducted an empirical review over a 24-year period to assess whether race and ethnicity
were related to the diagnosis of psychiatric disorders. Research showed a clear pattern
wherein African Americans displayed a long-term increased rate of schizophrenia
diagnoses, often three to four times higher than the rate for Euro-Americans (Eack et al.,
2012; Schwartz & Blankenship, 2014).
Compared with Caucasians, mentally ill African Americans have more chronic
disease, higher rates of inpatient service use, lower rates of outpatient mental health
service use, and more barriers in seeking mental health treatment (Avent, Cashwell, &
Brown-Jeffy, 2015; Change et al., 2013; Corrigan et al., 2014; Copeland & Snyder, 2011;
Ward et al., 2013). Noonan, Velasco-Mondragon, and Wagner (2016) further examined

the statistics regarding the medical and mental health of African Americans. The authors
reported that, African Americans are the least healthy group in US society (i.e., medical
illness, death rates, mental health) and numerous disparities exist in African Americans’
ability to access and use various health resources, including mental health resources.
African Americans are also the poorest ethnic group in the USA and poverty has been
highly correlated with poor health outcomes, increased morbidity, and increased
mortality (Noonan et al., 2016). In addition, it was reported that Black men and women
aged 20 years and older have the highest prevalence of hypertension, highest prevalence
of obesity, and highest rates of diabetes (National Center for Health Statistics, 2015;
Noonan et al., 2016). According to a 2014 report, Blacks have a 1.3 times greater rate of
having a non-fatal stroke, a 1.8-times greater rate of fatal stroke, a 1.5 times greater rate
of death attributable to heart disease, and a 4.2 times greater rate of end stage kidney
disease (Go As et al., 2014).
Gaston and Doherty (2017) recently completed a systematic analysis of 278
articles that focused on mental health and perceptions of care for mental health of
American and/or foreign-born Blacks who reside in the states. Results revealed that
African American’s negative perceptions of mental health and the mental health system
were identified as barriers to use of mental health services. Reasons for varying service
use included a lack of trust in their provider, the service providers competence, and the
clients’ perspectives as to whether or not the provider respected them. Findings for this
study were relevant for this study as they suggested that structural barriers such as
poverty, racism, discrimination, fear, and reliance on other coping mechanisms were also

identified as barriers to mental health seeking (Gaston & Doherty, 2017). In addition,
perception of racism and stigma were identified as barriers to seeking mental health
information (Gaston & Doherty, 2017).
Barriers to Seeking Help for Mental Illness Among African Americans
Researchers have identified several barriers that prevent African Americans from
seeking treatment for mental illness. Those major barriers are stigmas against mental
illness (Campbell & Mowbray, 2016; Drapalski et al., 2013) and negative attitudes
toward seeking professional help for their mental health concerns (Avent, Cashwell, &
Brown-Jeffy, 2015; Chang et al., 2013; Corrigan et al., 2014; Villatoro & Aneshensel,
2014). Additional literature related to each barrier is presented below.
African Americans and Stigmas Against Mental Health
Mental health stigma continues to have a strong impact on help seeking and
attitudes toward mental illness for African Americans. Campbell and Mowbray (2016)
completed a qualitative study to assess the impact of stigma among 17 African
Americans who had experienced depression. Results indicated that many African
Americans diagnosed with mental illness feared being viewed as being crazy or weak.
Participants reported hiding symptoms or neglecting to seek treatment to avoid being
labeled. Findings illustrated the impact of stigmatizing beliefs such as “You’re weak”
from being diagnosed with a mental health diagnosis on African Americans’ perceptions
and attitudes towards mental illness (Campbell & Mowbray, 2016).
Research has shown that stigmas against mental health stigma are common phenomena
surrounding a mental health diagnosis and treatment in general. Drapalski et al. (2013)

explored the prevalence of mental health stigma among 100 African Americans who had
a mental health diagnosis. Researchers used a structural equation modeling to examine
the relationships between internalized stigma, psychiatric symptoms, self- esteem, self-
efficacy, and recovery orientation. Greater internalized stigma was associated with lower
levels of self-esteem, self-efficacy, and recovery orientation, as well as with more severe
psychiatric symptoms (Drapalski et al., 2013).
By understanding how stigmas against mental illness serve as barriers to seeking
help for mental health issues among African Americans, professionals may be able to
develop more effective strategies for how to engage this population in therapeutic
services (Hall & Sandberg, 2012). Hall and Sandberg (2012) focused on mental health
stigma and whether stigmas contributed to barriers to mental health therapy among
African Americans. The authors conducted a phenomenological study of a sample of
eight participants. The authors found that stigma was a barrier to treatment among
African Americans. Furthermore, it was a trusting relationship with their mental health
provider that made a difference in patients’ willingness to continue therapy. Other
barriers to overcoming mental health treatment among African Americans included
individual personality traits, such as resilience, confidence, strong work ethic, open
mindedness, and independent thinking (Hall & Sandberg, 2012). This study was very
informative and applicable to my study, as it provided a detailed review of various
barriers to mental health care among African Americans. However, given that the study
only had eight participants, the results of the study were more difficult to generalize.

Within African American culture admitting one has mental illness is sometimes
viewed as a personal weakness (Campbell & Mowbray, 2016; Corrigan et al., 2014).
Researchers have shown that this perceived stigma could deter African Americans from
discussing their mental health with family members and from approaching professionals
concerning services to address issues related to mental illness (Alvidrez, Snowden, &
Kaiser, 2008; Conner et al., 2010; Copeland & Snyder, 2011; Corrigan et al., 2014;
George, Duran, & Norris, 2014; Masuda et al., 2012).
Haynes et al. (2017) conducted focus groups among African Americans from
rural settings, health care providers in those areas, and faith community representatives to
determine African Americans’ perceptions of mental health issues and stigma. The
authors found that among rural African Americans, mental health stigma was a barrier to
care. Results also indicated that barriers to the use of mental health services included lack
of awareness about mental illness, concerns about a lack of anonymity, and fears of being
labeled crazy. The authors advised community-based interventions, approaches, and
programs aimed at reducing mental health stigma among Americans in rural areas.
African Americans’ Attitudes as Barriers Toward Help Seeking for Mental Illness
Researchers have determined that African Americans tend to hold negative
attitudes toward seeking professional help for their mental health concerns (Avent,
Cashwell, & Brown-Jeffy, 2015; Chang et al., 2013; Corrigan et al., 2014; Villatoro &
Aneshensel, 2014; Ward et al., 2013; Watson & Hunter, 2015). Ward et al. (2013)
explored African Americans’ attitudes toward help seeking and mental health care,

preferred coping behaviors and whether variables differ by gender. The authors
conducted a cross-sectional analysis of a random sample of 272 young and middle-aged
African Americans. Participants reported serious barriers to care, such as stigmas
attached to mental health help seeking due to their negative views of seeking mental
health help. Results indicated that participants were not open to acknowledging
psychological problems and preferred religious coping methods instead of seeking
professional help. In addition, African American men were noted to be less open to
seeking professional mental health help in comparison to women. This study provided a
perspective as it relates to how mental health stigma can be a barrier for seeking mental
health treatment among African Americans and gender difference in seeking professional
help.
Research showed that the attitudes of African American women towards seeking
professional help for mental illness was positively associated with anxiety and depression
among the individuals (Watson & Hunter, 2015). Findings from a Watson and Hunter
(2015) quantitative study showed that African American women exhibited apprehensions
and anxiety when considering engagement in mental health services to address their
mental health concerns. Meaning, concerns about being negatively judged were more
associated with feelings of anxiety and worry. The more women endorsed stigma
concerns the less interested they were in seeking mental health treatment. The results of
the study indicated that African American women’s attitudes towards professional
helpseeking did not moderate the associations between anxiety or depression,
respectively. Watson and Hunter (2015) showed that there are specific barriers when it

comes to African Americans seeking mental health help (such as anxiety, etc.) that
should be taken into consideration (Avent, et al., 2015).
Research has demonstrated that African Americans typically have lower rates of
treatment seeking for mental health issues than Whites as well as higher dropout rates
from treatment and greater use of emergency care (i.e., inpatient care) for mental illness
(Avent et al., 2015; Awosan, Sandberg, & Hall, 2011; Brown et al., 2010; Watson &
Hunter, 2015). According to SAMSHA (2015) the adults most likely to use mental health
services in 2014, (17.1%) were in the group reporting two or more races, followed by
White adults (16.6%), American Indian or Alaska Native adults (15.6%), followed by
African Americans (8.6), Hispanic (7.3), and Asian (4.9%) adults. According to Avent et
al. (2015), only 15.7% of African Americans diagnosed with a mood disorder sought
help from a mental health specialist, and only 12.6% of African Americans diagnosed
with anxiety disorders sought treatment for their mental health issues. White adults
diagnosed with a serious mental health disorder were less likely to use emergency
services such as inpatient mental health services compared with African American adults
(7.4% vs.
11.3%; SAMSHA, 2015).
Other factors which are associated with reduced help seeking among African
Americans include poverty, lack of access to services or transportation to treatment,
racial-ethnic mismatch with mental healthcare providers, and mistrust of providers
(Geroge, Duran, & Norris, 2014; Masuda et al., 2012; Watson & Hunter, 2015). In
addition, family influence and family history can have an indirect and direct influence on

the use of mental health treatment for African Americans. Villatoro and Aneshensel
(2014) conducted a quantitative, correlational study that examined the relationship
between family influences and subsequent utilization of mental health services among
African Americans. The study consisted of 605 individuals from the 2001-2003 National
Survey of American Life. Results indicated that individuals with family history of
untreated disorders are unlikely to use mental health services. Recent literature has also
indicated that African Americans are more likely to use mental health services when
there is some guidance present from a religious leader (Williams & Cabrera-Nguyen,
2016). Williams and Cabrera-Nguyen (2016) assessed 816 African American adults via
secondary analyses of data from the National Survey of American Life. Findings further
indicated that women were more likely than men to utilize mental health services in their
lifetime. Results from this study are relevant as it gives insight to the relationship
between the evaluated need for mental health service usage for this population and
illustrates another variable to consider that may be attributing to disparity in service
utilization for African Americans.
Researchers have further found that African Americans’ distrust of mental health
providers could be misinterpreted as clinical paranoia by clinicians; and such attitudes on
clinicians’ part could further aggravate African Americans’ distrust of mental health
professionals (Crosby, & Varela, 2014; Whaley, 2011). Cultural mistrust has been partly
attributed to differences in how African American and European American patients are
diagnosed (Whaley, 2011). For instance, Whaley (2011) examined the relationships
between demographic background, patients’ self-report of paranoid symptoms, and

patients’ self-report of cultural mistrust of clinicians’ ratings of cultural mistrust.
Findings indicated that clinicians approached African American and European patients
differently due to the patients’ distrust of providers that are not of the same ethnicity as
the individual (Whaley, 2011). Research demonstrates that mental health diagnosis and
treatment are more efficient when African American patients are seen by mental health
professionals who belong to the former’s same ethnic group (Stansbury, Peteson, &
Beecher, 2013; Topkaya, 2014; Williams, Bekcmann-Mendez, & Turkehimer, 2013).
Findings from past studies have revealed that African Americans prefer to be matched
with African American therapists because African Americans tend to evaluate therapists
of their own ethnic group more positively than therapists of other racial groups (Cabral &
Smith, 2011; Masuda et al., 2012).
Mental Help Seeking Among African American College Students
Findings from several studies have shown that African American college students
tend to be as distressed as college students from other ethnic backgrounds (Ayalon &
Young, 2009; Songtag-Padilla et al., 2016). However, results from other studies have
shown that African American college students are less likely to seek help from
professional mental health sources (Masuda, Anderson, Twohig et al., 2009; Masuda et
al., 2012). Masuda et al. (2012) conducted a quantitative study to assess whether mental
health stigma and self-concealment were related to attitudes toward seeking
psychological services for African American college students. Data were collected from
221 African American students through the use of several surveys. Results revealed that
mental health stigma and self-concealment were positively associated with help-seeking

attitudes after controlling for gender, age, and previous experience of seeking
professional psychological services (Masuda et al., 2012). Findings from this study
implicated that mental health stigma does attribute to one’s attitude towards help seeking,
particularly for African American students.
When it comes to attitudes and help-seeking behavior for African American
students attending HBCUs not much research has been conducted in this area. However,
Colvin, Bullock, and George (2016) completed a study to examine student’s attitudes
towards mental help-seeking behavior. This quantitative study consisted of 407 college
students attending an HBCU. Results showed statistically significant relationships
between student demographics in terms of age, gender, classification level, and students’
attitudes towards help-seeking (Colvin, Bullock & George, 2016). College students who
had been at the school longer showed more positive attitudes toward mental health
service utilization, which indicated that the more opportunity students had to be exposed
to university counseling centers and education, the more favorable their attitudes became
towards help seeking. In addition, gender was a significant factor that impacted mental
health help-seeking behavior. Results showed that female students tended to display
more positive attitudes towards help-seeking behaviors than male students (Colvin et al.,
2016). Mesidor and Sly (2014) explored the relationship between social cognitive
factors, psychological distress, and help seeking intentions for international and African
American college students. The social cognitive factors included in the study were
attitudes towards mental health help seeking, subjective norms, and perceived behavioral
control. Researchers used a quantitative research design, using correlational analyses to

examine 111 college students attending an HBCU and a Christian liberal arts university.
Findings indicated that perceived behavioral control (perceived capacity to seeking
mental health services) was the strongest predictor of help-seeking intentions among both
groups. In addition, results showed that attitudes toward mental health services were not
a significant predictor of mental health seeking intentions.
Ethnic Identity and Psychological Well-Being
Ethnic identity is a variable that influences ethnic minority groups, such as
African Americans’ help-seeking attitudes and behaviors toward mental illness (Watson
& Hunter, 2015; Yazici, Gul, Yazici, & Gul, 2016). Results from a study by Cheng et al.
(2013) revealed that African Americans who possessed high levels of ethnic identity had
decreased self-stigma toward seeking help for psychological issues. Limitations for this
study included the completion rate of surveys with useable data. Findings from this study
indicated that one’s ethnic identity could potentially impact treatment seeking behavior
for African American students with mental illnesses.
Researchers have also assessed whether individuals’ ethnic identity was related to
their well-being and perspectives of themselves. Smith and Silva (2011) conducted a
meta-analysis of 184 studies of a mixed ethnicity (African Americans, Asian Americans,
Hispanic Latino Americans, Native Americans, and Pacific Islander Americans) in the
U.S. This was a systematic review of research to assess the magnitude of the association
between ethnic identity and one’s well-being (i.e., self-esteem) and to determine if the
association is influenced by study (i.e., research design, location) and characteristics of
the participant (i.e., age, gender, education). Results indicated that ethnic identity was

minimally related to measures of mental health symptoms (i.e., anxiety or depression).
The researchers did not find any statistically significant differences in the relationship
between ethnic identity and measures of mental health symptoms across the various
ethnic groups. Limitation of this study included that the review of studies only contained
quantitative studies.
Ajibade et al. (2016) found that ethnic identity and religious commitment were
positively associated with life satisfaction and psychological well-being. This survey
research design consisted of 189 African Americans, with majority of the sample being
females which limited the generalizability of the results. Results revealed that ethnic
identity was positively related with satisfaction and meaning with life. Findings from this
study are relevant to my study because the results showed how one’s ethnic identity or
cultural background was related to psychological well-being.
Hardeman et al. (2016) explored the relationship between ethnic identity and
well-being for African American medical students. The longitudinal survey research
study consisted of 301 African American students in their first year of training. Results
showed that first year African American medical students who had lower levels of ethnic
identity were less likely to experience depressive and anxiety symptoms in their first year
of medical school (Hardeman et al., 2016). These results are contrary to literature
demonstrating the role of one’s ethnic identity on their mental health. The study noted
above, concluded that African American medical students, in a predominantly White
school setting, with high ethnic identity may not have the necessary racial supportive
network needed with others because their racial identity is not shared among their peers

(Hardeman et al., 2016). Researchers indicated that African American students with high
ethnic identity may face greater challenges in fitting in with medical student identity
characterized by a White majority (Hardeman et al., 2016). This study revealed that one’s
ethnic identity and identification with the university’s setting race (i.e., predominantly
White or predominantly Black) can impact their experiences and symptoms of mental
illness differently.
Racial identity refers to the psychological meaning one makes of one's racial
group membership (Forsyth & Carter, 2012). An individual psychologically identifies
with or chooses not to identify with one’s racial/ethnic group. This includes the
emotional, behavioral, and cognitive expressions of their identity or group they identify
with (Cheng et al., 2013; Forsyth & Carter, 2012; Hooper et al., 2012). Hughes, Kiecolt,
Keith, and Demo (2015) explored the importance of one’s ethnic/racial identity and its
impact on one’s psychological well-being and mental health. Data were collected from
3,570 African Americans from the National Survey of American Life. Results indicated
that those who identified more with their own racial group and viewed their racial
identity as positively having a higher sense of self-esteem and fewer depressive
symptoms (Hughes et al., 2015). Limitations from this study included that authors
wanted to use different measures of racial identity for the study. Findings from this study
illustrated how one’s ethnic identity can impact one’s psychological well-being and
mental health.
Hooper et al. (2012) studied the effect of ethnic identity on depressive
symptomology and trust in the mental health system by White and African American

students. The researchers found that ethnic identity explained some of the variability in
the symptoms of depression in African American students but not White college
students.
The researchers further implied that cultural identification with a mental health provider
was critical in African American college students’ seeking of mental health treatment.
In another study, where Britian et al. (2013) assessed the association between
ethnic identity and mental health. The researchers found that higher levels of ethnic
affirmation (i.e., positive perception of ethnicity) for African American college students
predicted better mental health. Results showed that higher levels of ethnic affirmation
also predicted less anxiety and fewer depressive symptoms among African American
college students. In that study, 3,659 college students representing Latino, Asian, and
African Americans were surveyed to assess whether stronger ethnic identity promoted
positive mental health. Findings from the study illustrated the importance of assessing
the association between ethnic identity and mental health in order to promote better
mental health among African American students
A few researchers have investigated how various forms of personal identity, such
as racial or ethnic identity, mediates the relationships between mental health outcomes
and preferences for particular strategies for coping with mental illness (Forsyth & Carter,
2012; Hughes et a., 2015; Molina & James, 2016; Pieterse & Carter, 2010). Strong ethnic
identity has been linked to a range of positive psychological outcomes among individuals
from diverse racial backgrounds (Brittian et al., 2013; Hooper, et al., 2012; Smith &
Silva, 2011). However, research on the relationship between racial identity status and

mental health issues for ethnic groups is sparse and contradictory (Fischer et al., 2014).
As with much of the published stigma related work, researchers have generally used
predominantly White individuals or did not specifically focus on ones’ ethnic identity as
a factor for treatment seeking behavior. Therefore, the degree to which findings from
those studies can be generalized to African American populations or specifically to
students attending HBCUs is unclear (Alvidrez et al., 2010; Brittian et al., 2013; Cheng
et al., 2013). Further research was necessary to understand the phenomenology of
African American students' ethnic identity and experiences as they are related to their
attitudes about seeking mental health services.
Summary
People who suffer from mental illness and other mental health problems are
among the most stigmatized, discriminated against, marginalized, disadvantaged, and
vulnerable members of our society (Ilic et al., 2013). Mental health issues in college
students is an ongoing concern for colleges and universities (Schoen, & McKelley,
2012). Mental illness stigma is a major barrier to seeking professional help for
individuals with mental illness and their families (Alonso et al., 2009), increasing the
impact of mental illness on society (Rüsch, Todd, Bodenhausen, & Corrigan, 2010).
Moreover, African Americans have relatively high rates of mental disorders that
carry substantial need for treatment (Villatoro & Aneshensel, 2014). Findings from past
research has shown that culture influences mental health treatment in many ways,
including the identification and manifestation of symptoms, verbal and nonverbal
communication regarding mental illness, help-seeking behavior, stigma, and shame

associated with mental illness or treatment (Ashley, 2014). These cultural factors can
also influence the client’s attitudes, adherence, and response to treatment (Ashley, 2014).
Because one’s ethnic identity can influence help-seeking attitudes, examining
how African American college students’ ethnic identity is related to their attitude about
mental illness can lead to a better understanding of factors or variables related to help
seeking for mental illness in this population (Cheng et al., 2013; Fuller-Rowell et al.,
2011; Hooper et al., 2012). Such information could potentially shed light on how ethnic
identity may be a mediating factor of mental illness that adversely affects African
American college students’ adjustment to college. With this knowledge human services
professionals, college administrators, college counselors, and other professionals could
potentially develop outreach programs that strengthen ethnic identity and encourage help
seeking for mental illness.
The following chapter further explains the methodology employed to assess the
predictive relationships identified between stigma of mental illness, perceptions of
mental illness, attitudes towards help seeking, and ethnic identity. Chapter 3 entails a
description of the research methodology and design that were used in this study. Chapter
3 also details the sampling method, recruitment procedures, and targeted participants.
The data collection methods and data analysis plan are also outlined. In Chapter 3, the
research ethical guidelines and ethical considerations are also clarified.

Chapter 3: Research Method
Introduction
The purpose of this quantitative, nonexperimental, correlational study was to
investigate the predictive relationships between ethnic identity, perceptions of mental
illness, stigma of mental illness, and attitudes toward seeking professional help for
mental illness among African American college students attending HBCUs. In this
chapter, I present details of the research design, rationale, the methodology, and
justification for the chosen design. In the methodology, I further discuss the population,
sampling methods, procedures for recruitment, instrumentation, and operationalization of
variables. In this chapter, I further include an overview of threats to validity as well as
identify ethical issues that were taken into consideration for this chapter. I conclude with
a summary of the research methodology that was used for this study.
Research Design and Rationale
I used a quantitative, nonexperimental, cross-sectional, survey methodology to
examine the relationship between ethnic identity, perceptions of mental illness, stigma of
mental illness, and attitudes toward seeking professional help for mental illness among
African American college students. A quantitative research design’s primary goal is to
analyze and represent relationships between variables mathematically through statistical
analysis. Quantitative research is an objective process used to describe variables,
examine relationships, and determine cause and effect interactions among variables
(Babbie,
2010). In quantitative research, data are collected at a single point in time (Creswell,

2013; Rahman, 2016). Quantitative research also allows for generalizations that can be
applied to the greater population (Quick & Hall, 2015). For the purpose of this study, a
quantitative, cross-sectional design was chosen. A cross-sectional study was ideal for this
study as cross-sectional studies can be conducted relatively fast and they are inexpensive
to conduct (see Setia, 2016). These types of studies are also appropriate for
populationbased surveys. In addition, a cross-sectional design was chosen because
quantitative research can be used to examine the relationships between variables (see
Creswell, 2013; Quick & Hall, 2015; Rahman, 2016). For this reason, a quantitative
research design was appropriate for my study because I examined the predictive
relationships between ethnic identity, perceptions of mental illness, and attitudes towards
seeking professional help for mental health issues among African American college
students after controlling for gender.
A survey design was the preferred type of data collection procedure for this study
because this method provided a quantitative description of trends or attitudes of a
particular population (see Creswell, 2013; Rahman, 2016). The simplicity of the design
and fast turnaround in data collection is also an advantage in using this design (Creswell,
2013; Rahman, 2016). Using an online survey tool such as SurveyMonkey allowed me to
download the data into a spreadsheet or a database that could be uploaded into SPSS for
further analysis. In addition, using an online survey kept participants from skipping
questions by not allowing them to continue with the survey until the completion of each
question. The data were further analyzed using a multiple regression analysis. Multiple
regression analysis is a multivariate statistical technique that examines the relationship

between continuously distributed independent variables and one continuously distributed
dependent variable (Creswell, 2013; Lalwni et al., 2013).
Although other methods have been considered, they were eventually rejected.
When it comes to using a quantitative approach, there are two primary designs that are
used. The experimental design usually involves the introduction and manipulation of a
variable, and the nonexperimental approach uses data gathered from preexisting patients
and allows the researcher to explore relationships between variables (Onwuegbuzie,
2000; Quick & Hall, 2015). For this reason, I used a nonexperimental approach as I did
not manipulate any independent variables, a control or comparison group was not used,
and there was not a random assignment of participants to groups (see Onwuegbuzie,
2000; Rahman, 2016). A qualitative approach was not considered for this study because
my interest was in examining the statistical relationship of these constructs rather than
developing descriptions and themes from the data.
Methodology
Population
The targeted population for this study were African American college students
attending HBCUs in the Atlanta, GA, area. The approximate size of the population of
African American students attending HBCUs in the Atlanta, GA, area is currently
estimated at 7,810 (National Association for College Admission Counseling, n.d.). These
data are based on students enrolled at Spelman College, Morehouse College, Clark
Atlanta University, and Morris Brown College.

Sampling and Sampling Procedures
The convenience sampling strategy and snowball sampling were used to recruit
participants for this study. I chose a convenience sample because participants were
recruited based on convenience and availability (see Creswell, 2013). Snowball sampling
was also used to assist with the difficulty in recruiting participants to participate in this
research. Snowball sampling allows for research participants to recruit other participants
for a test (Statistics How To, 2015). The inclusion criteria for the study were that
participants had to be traditional African American college students between the ages of
18 and 23 years (Crisp, 2013; Wilsey, 2013) currently enrolled in one of the targeted
HBCUs in Atlanta, GA. Students either attending an online, hybrid, or traditional
classroom course were included in this study.
A power analysis was conducted to determine the optimal sample size required to
detect meaningful differences in the data with a given effect size and degree of
confidence (Faul, Erdfelder, Buchner, & Lang, 2009). The tool that I used to calculate
the sample size is the G*Power, which provides for both numerical and graphical output
options (Faul et al., 2009). The G * Power program calculates power analyses for many
different statistical tests (Faul et al., 2009). This calculation was completed using a
medium effect size (f2) of .15, an alpha 0.05, a power of 0.80, and a two-tailed test. The
results indicated that the minimum sample size needed to have adequate power to detect
differences in the data when using a logistic regression was N = 77.

Procedures for Recruitment
In order to recruit participants for the study, I first obtained institutional review
board (IRB) approval from Walden University. I also contacted the Atlanta universities
from which the students were recruited to determine whether separate IRB approval was
required to actively recruit participants from their campuses. Recruitment for participants
began after approval had been received from the IRB of Walden University and
permission was granted to conduct research at each participating university. After
Walden IRB approval was granted, each HBCU was contacted to obtain the university’s
IRB approval in order to obtain permission and to begin recruitment for the study. Once
IRB approval was obtained, Morehouse’s Communication Department, Spelman’s
College Psychology Department, and the Clark Atlanta University’s Social Work
Department were contacted to assist in recruiting and emailing students who were
interested in becoming volunteers for this study.
Participants were invited to participate in the study through either an email or
flyer announcement. Morehouse College required communication for approval of flyers
to go through their communications department. Spelman College and Clark Atlanta
University required that the sponsoring faculty members assist me in getting
communication to students attending their institutions. The sponsoring faculty members’
role was advisory, which meant that faculty would provide guidance in recruiting
participants, ensuring that the institution’s research protocol was followed when
conducting studies with campus students, answering questions about the university’s
research protocols, and providing answers for questions that may arise at institution

during the recruitment process. The email announcement gave a brief introduction and
purpose of the study. The announcement also included eligibility requirements, contact
information, and a direct link to access the survey for those who were interested in
participating in the study. Because the survey was administered online, the students did
not have to take class time to complete the surveys; students completed the surveys on
their own time. In addition, I recruited college students through approved recruitment
flyers posted throughout the campuses and on social media (Instagram and Facebook).
The flyers provided instructions on how to participate in the study. Recruitment flyers
were posted after approval had been granted from each campus. The email and
recruitment flyer informed potential participants of the purpose of the research study.
Participation
Participation for this study was completely voluntary. All participants were
informed of their right to withdraw their consent or decline to participate in the study. A
direct link to the online survey platform, SurveyMonkey.com, was included in the
recruitment flyer and email announcement. The SurveyMonkey site included a screening
survey in order to eliminate participants who did not qualify for the study (See Appendix
A). The screening survey was used to screen for participant eligibility for participating in
the research. This screening survey was the first information that participants
encountered when they gained access to the survey. The screening survey asked whether
participants met each item of the inclusion criteria. If a participant failed to meet any
item of the eligibility criteria, the participant was automatically exited from the survey
using skip logic. After the screening survey, SurveyMonkey included direct access to the

demographic questionnaire and informed consent form, which had to be acknowledged in
order for interested participants to move forward with the study. Participants were
required to acknowledge that they read and agreed to participate in the study before being
able to move on to the next page, indicating the informed consent had been read.
Participants were informed that there were not any follow up sessions or need to contact
participants once the survey was completed. Participants were given instructions on the
informed consent form as to how they could also obtain results of the study, if interested,
after the survey was completed. A brief one to two-page summary of the results will be
emailed to each participating institution’s research, sponsoring faculty member, and IRB
department once the study is completed and posted only on the approved participating
institution’s Facebook page after the study has been completed and my dissertation is
approved. This information will be sent via email provided by me.
Data Collection
I obtained IRB approval (02-12-19-0350743) from Walden University to conduct
this research. I then obtained separate IRB approval from all three Atlanta universities
(i.e., Spelman College, Morehouse College, Clark Atlanta University) from which the
students were recruited. Permission to use the Attitudes to Mental Illness Questionnaire
(AMIQ) was obtained from the Royal College of Psychiatrists, who holds the copyright
for the AMIQ. Permission to use the AMIQ can be found in Appendix E. Permission to
use the Multi-Group Ethnic Identity Measure (MEIM-R) scale was not required,
according to Phinney (1992). Permission to use the Attitudes Toward Seeking

Professional Psychological Help (ATSPPHS) scale was not required. The publishers of
the ATSPPHS allow the measure to be used for educational purposes without obtaining
written permission (Fischer & Turner, 1970). Permission to use the Self-Stigma of
Mental Illness Scale (SSOMI) was not required. In addition, according to PsychTests,
permission is not required to use the ATSPHHS, SSOMI, or MEIM-R scale according to
the statement below:
Test content may be reproduced and used for non-commercial research and
educational purposes without seeking written permission. Distribution must be
controlled, meaning only to the participants engaged in the research or enrolled in
the educational activity. Any other type of reproduction or distribution of test
content is not authorized without written permission from the author and
publisher. Always include a credit line that contains the source citation and
copyright owner when writing about or using any test.
Participants were not paid for taking part in this study. Participation in the study
was completely voluntarily. Upon recruitment of participants, I provided participants
with a written explanation of the study via email, recruitment flyer, or social media. Each
method of recruitment included a direct line to access SurveyMonkey.com which
included the screening survey, informed consent form, participant eligibility
requirements, the demographic survey, and four survey instruments. Research related
documents were provided online for each participant to access on the SurveyMonkey
site. The screening survey was used, along with the demographic survey as barriers in
disqualifying participants who are not eligible to participate in the survey. In addition,

the letter of introduction explaining the study, found in the informed consent, was
provided on the SurveyMonkey website, which had to be accepted before participants
were able to access the survey. The online survey took approximately 15 minutes to
complete.
Demographic information collected for this study included age, date of birth,
gender, race, college degree/major, socioeconomic background, and participant’s
academic classification in college. See Appendix C for a copy of the demographic
survey. Responses to the demographic data were coded to ease in inputting information
into SPSS (See Appendix D). Personally, identifying information (such as one’s social
security, first and last name) was not gathered in the demographic questionnaire or on the
survey instruments. Participants were informed that they could exit the online surveys at
any time and without any penalty. Collected data was transferred to SPSS for data
analysis purposes and stored according to Walden University requirements. All data
accessed was downloaded into secure files protected by passwords. All electronic copies
of any data related to the study were placed in a separate folder on my computer
protected by a password, with its own password that only I have access to and backed up
on a password-protected hard drive.
Instrumentation and Operationalization of Constructs
All variables in this study are constructs and hence were measured by a specific
instrument that had been developed to specifically provide concrete, feasible,
quantifiable information about each construct. In this study, the independent variables
were ethnic identity, stigma of mental illness, and perceptions of mental illness. Ethnic

identity was measured by the scores on the Multigroup Ethnic Identity Measure Scale
(See Appendix E). Variables on this scale were measured on an ordinal level. Attitudes
toward mental illness was measured by scores on the AMIQ (See Appendix F). Stigma
against mental illness was measured using the SSOMI (See Appendix G). The dependent
variable in this study was attitudes toward seeking help for mental illness, which was
measured by scores on the ATSPPHS (See Appendix H).
Ethnic Identity
Ethnic identity was operationalized by using scores on the Revised Multigroup
Ethnic Identity Measure (MEIM-R). Permission to use the MEIM-R scale was not
required according to Phinney (1992). See Appendix E for a copy of the instrument.
Phinney (1992) saw the need to explore the meaning of one’s ethnic identity and sense of
belonging as it relates to the identity of an adolescence, and more specifically to their
self-concept, hence the instrument was developed. Phinney (1992) stated that no
permission was needed to use this instrument; hence, no permission document was
necessary for this instrument. The MEIM Scale was developed by Phinney in 1992 to
assess one’s internalized meaning of one’s ethnic group membership. The MEIM
instrument measured how well someone related to a certain ethnic identity. This scale
was developed to use various subscales (ethnic identity achievement,
affirmation/belonging, ethnic behaviors, other group orientation) to explore internalized
meaning of one’s ethnic group membership). The original subscales were called Ethnic
Identity Search Subscale and the Affirmation, Belonging, and Commitment Subscale.

The original MEIM instrument had a total of 14 items that related to one’s
selfcategorization with a given ethnicity. The subscale of ethnic identity search related to
items 1, 2, 4, 8, and 10; the subscale of affirmation, belonging, and commitment was
measured by items 3, 5, 6, 7, 9, 11, 12; the last three items are items directed at
identification by ethnicity (items 13, 14). Each item was scored on a Likert scale from 1
to 4, with the following breakdown: (4) Strongly agree; (3) Agree; (2) Disagree; (1)
Strongly disagree. Phinney and Ong (2007) recommended using the mean scores for the
total score and for the individual subsection scores.
Roberts et al. (1999) completed a large study consisting of 5,423 adolescents
consisting of various ethnic groups in the Southwestern United States. Roberts and
colleagues found that two negatively worded items in the initial MEIM did not fit the
model that MEIM predicted (Phinney & Ong, 2007). This analyses further led to the
removal of two ethnic behavior items and rewording some items to increase face validity
of the scale. With these 2 items removed, the remaining 12 items represented the two
factors, exploration (5 items), and commitment (7 items). Soon after thorough
psychometric testing, the original MEIM was revised and the instrument is now called
the MEIM-R. The original MEIM was revised because of concerns regarding the validity
of the instrument. Phinney and Ong (2007) were led to make revisions of the MEIM to
improve the face validity and content validity after obtaining results from a conflicting
factor analysis of the original MEIM. Hence, the researchers conducted various focus
groups and interviews to examine the appropriateness of items for measuring ethnic
identity in diverse minority youth. This, in turn, led to the two-factor model

implementation and revision of a 6-item MEIM-R scale (Phinney & Ong, 2007). Yoon
(2011) later assessed the construct validity of the MEIM-R using confirmatory factor
analyses. Results indicated construct validity for a two-factor structure (i.e., exploration
and commitment) of the MEIM-R.
The MEIM-R also consisted of two main factors (exploration and commitment
subscales) (Phinney & Ong, 2007). Since psychometric properties of MEIM-R have been
tested numerous times in various settings, in different studies these two factors are
occasionally referenced using different terms. Most commonly, the two factors are called
ethnic identity exploration and ethnic identity commitment (Worrell, Conyers, Mpofu, &
Vandiver, 2006). This questionnaire is composed of items that are rated on a 5-point
Likert-type scale, with answers ranging from 1 = Strongly Disagree 2- Disagree 3=
Neutral 4= Agree to 5 = Strongly Agree for each item. Subscale scores for each category
in this measure can be broken down as follows: items 1, 4, and 5, assess exploration;
items 2, 3, and 6, assess commitment. Sample items on the MEIM-R include “I have
often talked to other people in order to learn more about my ethnic group” and “I feel a
strong attachment towards my own ethnic group”. Phinney and Ong recommended using
a total score of the instrument for a total score on the ethnic identity measure. The total
scores on each individual subscale are used for a more precise measurement on ethnic
identity exploration and ethnic identity commitment.
Higher MEIM commitment scores indicate positive affirmation of one’s group
and a sense of commitment to that group. Higher exploration scores indicate greater
engagement in learning about one’s group and participation in ethnic cultural practices

(Phinney & Ong, 2007). Sample items on the MEIM include “I have often talked to other
people in order to learn more about my ethnic group” and “I feel a strong attachment
towards my own ethnic group.” Higher scores on the scale overall indicates higher
belonging to one’s ethnic identity. This MEIM-R is appropriate for this study and for
measurement of this variable because it was specifically developed to address the need
for measuring ethnic identity in various populations.
Reliability of MEIM-R. Cronbach’s α is the most commonly used test to
determine the internal consistency or reliability of an instrument (Heale & Twycross,
2015). Cronbach’s alpha measures how closely related items in a given set are to each
other. The values for Cronbach’s alpha measurement are measured from 0 to 1. Values
that are closer the value to 1.0 for a scale indicates the items in a given set are related
closely, which indicates that items on the scale or instrument have high internal
consistency (Anderson, Gerbing, & Hunter, 1987). The MEIM scale has very good
internal reliability as shown by numerous studies which explored the instrument’s
psychometric properties. The original coefficient alphas for the school sample where the
instrument was validated were reported to be in the 0.8 range (Phinney, 1992). Prior
research in primarily college student samples has also indicated good reliability, with
internal consistency (Cronbach’s) ranging from .76 to .91 for the two subscales and .81
to .89 for the overall scale (Brown et al., 2014; Phinney & Ong, 2007; Yoon, 2011). High
reliability means that the scale has a high chance of producing similar results when used
again and again for various studies (Heale & Twycross, 2015). This scale has been used

in quite a few studies and has consistently shown good reliability across a wide range of
ethnic groups and ages.
The MEIM-R scale has been used before in multiple studies that included ethnic
identity as one of the variables. For example, Yoon (2011) conducted a survey of 289
California students to confirm the validity and reliability of the MEIM-R. Results
indicated excellent reliability coefficients for both groups, with values ranging from .84
to .91 (Yoon, 2011). In more ethnicity-specific testing, alphas were examined for the
MEIM-R scale in European Americans and minorities. In European Americans, alphas
for the MEIM-R were reported as .89 and in minorities, .88. (Yoon, 2011).
Homma, Zumbo, Saewyc, and Wong (2014) conducted a study of 4150 East
Asian teenagers in Canada using the MEIM-R in order to study the instrument’s
psychometric properties. The researchers conducted a reliability analysis and found that
the instrument had very good overall internal consistency reliability -- Cronbach’s alpha
was 0.88 (Homma et al. 2014). When Homma et al. analyzed the factor structure of the
MEIM-R through factor analysis, the analysis did yield (confirm) the presence of two
factors: exploration and commitment. The Cronbach’s alpha for the exploration factor
was 0.76 (medium strength) and the Cronbach’s alpha for the commitment factor was
found to be 0.84 (very strong).
Brown et al. (2014) addressed gaps in the psychometric literature on the MEIM-R
by evaluating properties such as factor structure, measurement invariance, and internal
consistency across multiple groups (i.e., Asian, Black/African Americans, Hispanic, etc.)
and for women. The researchers reported that results from their study supported the

previously reported values for the psychometric properties of the MEIM-R. The
researchers further concluded that MEIM-R could be used to make comparisons across
multiple racial and ethnic groups (Brown et al., 2014). Results from the study mentioned,
indicated that internal consistency in each modality was good; all subscale and overall
scale values for Cronbach’s α were near or above .70 (Brown et al., 2014). Herrington et
al. (2016) further evaluated the reliability of the MEIM-R across 37 studies and
compared the results with the reliability of the original MEIM that was evaluated across
75 studies. Results indicated that reliability coefficients for the MEIM-R averaged .88
across 37 samples, which was a statistically significant increase over the average of .84
for the MEIM across 75 studies (Herrington et al., 2016). However, the authors warned
that for individuals of lower socioeconomic backgrounds and for individuals with lower
levels of education, the reliability coefficients tended to be somewhat lower, averaging at
around 0.77. Herrington et al. (2016) suggested that the results from MEIM should be
interpreted with caution when studying ethnic identity in younger students and in those
who come from disadvantaged backgrounds.
Chakawa, Butler, and Shapiro (2015) also found that reliability scores for MEIM-
R tended to be slightly lower in minorities. The authors conducted a study on 207 adults.
The authors tested participants’ ethnic identity using the MEIM-R scale. The findings
indicate that in the full sample -- in European Americans and in African Americans -- the
reliability alpha was 0.81 for both the exploration and for the commitment scales.
However, when only scores from African American participants were analyzed, the
reliability scores for the two scales dropped to 0.70 and 0.76, respectively.

Musso, Moscardino, and Inguglia (2017) also found that the MEIM-R tool has
high reliability. The authors conducted a study of 1,445 Italian school students. Per the
sample, the reliability alphas were 0.85 for the exploration subscale and 0.90 for the
commitment subscale. When stratified by participants’ backgrounds, exploration
subscale showed a reliability of 0.83 and the commitment subscale of 0.91 for Italian
students, 0.87 and 0.92, respectively, for East European students, 0.83 and 0.82,
respectively, for North African students.
Validity of MEIM-R. Validity is defined as the extent to which a concept is
accurately measured in a quantitative study (Heale & Twycross, 2015). The construct
validity of the MEIM scale has been measured overtime. However, the original MEIM
was revised more than once because of concerns of validity. Phinney and Ong (2007)
were led to make revisions of the MEIM to assess face validity and content validity after
obtaining results from a conflicting factor analyses of the original MEIM (Herrington,
2008). Hence, researchers conducted various focus groups and interviews to examine the
appropriateness of items for diverse minority youth. This, in turn, led to the two-factor
model implementation and revision of the MEIM (Phinney & Ong, 2007). Homma et al.
(2014) analyzed the factor structure of the MEIM-R through factor analysis. The
researchers found that the factor analysis did yield (confirm) the presence of two factors:
exploration and commitment.
Worrell, Conyers, Mpofu, and Vandiver (2006) conducted a study of 211
secondary school students in Zimbabwe to assess structural validity of the MEIM-R
instrument. The authors found that the construct validity of the instrument was 0.82. No

other types of validity were measured in that study. Miyoshi, Asner-Self, Yanyan, and
Koran (2016) examined the MEIM-R tool closely for various types of validity using a
sample of Japanese sojourners. The authors found high construct validity for the
instrument, even though they found high convergent validity and medium discriminant
validity (alpha of 0.56). This means that according to this specific study, the MEIM-R
instrument does measure some amount of something else that it is not supposed to
measure.
Perception of Mental Illness
Perceptions of mental illness is an independent variable that was measured using
the AMIQ (See Appendix F). Permission to use the AMIQ was obtained from the Royal
College of Psychiatrists and can be found in Appendix E. This instrument measured
people’s attitudes toward mental illness, and hence this instrument is directly applicable
to this study. The instrument was first developed by Cunningham, Sobell, and Chow
(1993). This initial study was assessed with 579 participants attending the Ontario
science center. Vignette questions used for the study were reflective of a hypothetical
substance user and participants were randomly assigned to one of six scenario conditions.
This study sought to address people’s beliefs about appropriateness of self-change,
moderate drinking outcomes, degrees of credibility attributed to substance abuser and
recovery and beliefs associate with abuse of different substances (Cunningham, Sobell,
& Chow (1993). The AMIQ consists of five short vignettes that describe an imaginary,
stigmatized individual with mental illness. Each vignette has 5 questions that assess
individuals’ perceptions of the subject of the vignette and their willingness to interact

with the individual. Each question is scored on a scale of -2 to +2. The total scores for
each vignette can range from -10 to +10. The total score for a vignette would be a -10, if
each of the five items is scored as “-2” by a participant. The total score would be a +10,
if each question is scored as a “+2” by participants. Higher scores on the measure
indicate a more favorable view of mental illness on the part of the individual completing
the questionnaire. Lower scores indicated more negative attitudes towards mental illness.
Thus, a score on the higher range closer to +10 on the instrument indicates that someone
who completed the scale has the most favorable view of mental illness as possible by the
scale. For the purpose of this study, only one vignette was utilized to assess participants
perception of mental illness.
Reliability of the AMIQ. The AMIQ is a short instrument survey that has shown
good stability, test-retest reliability, and alternative test reliability. Luty, Fakuda, Umoh,
and Gallagher (2006) developed the AMIQ to assess peoples’ attitudes individuals with
mental illness. The standardization sample consisted of 1,079 adult participants in the
United Kingdom. The researchers reported good reliability as evidenced by with
Cronbach’s alpha of .93 and test-retest reliability r = 0.704. Varghgughese and Luty
(2010) assessed the reliability of the AMIQ using a sample of 50 participants who were
asked to complete Corrigan’s Attributions Questionnaire, a previously validated measure
of stigmatized attitudes towards people with mental illness and AMIQ. The obtained
Spearman’s rank correlation rho=0.704 indicated good alternative test reliability. Theriot
and Lodato (2012) completed a study comparing attitudes toward mental illness and

perceptions of professional danger among 64 new social work students and 111 other
college students. The results generated Cronbach’s alpha for the AMIQ that ranged from
.67 to .81.
Validity of the AMIQ. In researching for different types of validity for the
AMIQ, there were only a few studies that assessed various types of validity (i.e.,
discriminant, construct, face, criterion validity). The majority of articles did not report
validity data from the study. Luty et al. (2006) reported that the instrument had good
construct validity with 80.2% of the variance being accounted for during factory analysis.
In the article by Luty et al. (2010) reported that other research has shown discriminant
validity, within accuracy of 77%. This value was calculated based on using a cut-off
AMIQ score of 0 for (participants in the study) pharmacists prepared to dispense
methadone to people with opiate dependence and pharmacists who were not.
Shah, Solanki, Vankar, and Parikh (2017) reported that the instrument’s
construct validity was very high, 0.933. The instrument contains vignettes that describe
highly stigmatized individuals (such as a convicted criminal); such vignettes produce
consistently negative scores and those describing non-stigmatized individuals (a
Christian and a diabetic) produce positive scores, indicating good face validity (Shah,
Solanki, Vankar, & Parikh, 2017). The authors did not specify values for construct
validity. Using the instrument to assess attitudes towards mental illness in medical
students, Balhara, Yadav, Arya, and Kataria (2012) stated that the instrument has high
construct and face validity as well, even though the authors did not specify the actual
values for the construct and face validity. In assessing previous research studies that have

utilized the AMIQ scale, there was a limited amount of information pertaining to the
validity and reliability of the instrument. Most studies either did not report specific
values or test for the reliability and/or validity of the AMIQ. Therefore, this research
study assessing the stigma of mental illness for African American college students
assessed the reliability and validity for the sample of participants recruited for this study.
Help-Seeking for Mental Illness
The dependent variable in this study is help seeking for mental illness. This
variable was be measured using the Attitudes Toward Seeking Professional
Psychological
Help Scale (ATSPPHS), which was originally developed by Fisher and Turner (1970;
See Appendix H). Permission to use the ATSPPHS scale was not required by the
publishers of this instrument. The ATSPPHS scale is used to assess one’s attitude toward
and willingness to seek mental health treatment from a professional mental health
provider. This 29-item scale was also shortened into a 10-item unidimensional version of
Fischer and Turner known as the abbreviated version of ATSPPHS-SF (Fischer &
Farina, 1995). For the purpose of this study, the original ATSPPH scale was used.
Items on the ATSPPHS scale are scored on a 4-point Likert scale that ranges from
0 = disagree to 3 = agree. There are 18 negative items that are reversed coded before
scoring the instrument (0 = agree to 3 = disagree). To determine a total score items 1, 3,
4, 6, 8-10, 13-15, 17, 19-22, 24, 26, & 29 are first reverse coded. Then points for the
individual 29 responses are summed up to obtain a total score. Low scorers (29-49),
express negative attitudes towards seeking help for themselves or significant others,

medium scorers (50-63), acknowledge that professional help can be useful but are unsure
about their willingness to use it, and high scorers (64-87) express positive attitudes
towards seeking and using professional help (Nyavanga & Barasa, 2016; Suradi, 2010).
The highest possible score is 87 (29 questions times a maximum three points for a given
item; See Appendix H for the ATSPPHS coding legend). A higher score reflects a more
positive attitude toward seeking professional assistance. An example item asked on the
questionnaire is: “The idea of talking about problems with a psychologist strikes me as a
poor way to get rid of emotional conflicts.” (Hammer, Parent, & Spiker, 2018).
The ATSPPHS scale is broken down into the following four subscales:
recognition of need for psychotherapeutic help, stigma tolerance, interpersonal openness,
and confidence in mental health practitioners (Hammer, Parent, & Spiker, 2018).
Questions 4, 5, 6, 9, 18, 24, 25, 26 are assigned to the Recognition of Need for
Psychotherapeutic Help Subscale. Questions 3, 14, 20, 27, 28 are assigned to the Stigma
Tolerance Subscale. Questions 7, 10, 13, 17, 21, 22, 29 are assigned to the interpersonal
openness Subscale. Questions 1, 2, 8, 11, 12, 15, 16, 19, 23 are assigned to the
Confidence in Mental Health Practitioner Subscale.
Reliability of ATSPPHS. The original authors of the ATSPPHS reported good
internal reliability (α= 0.86) and test-retest reliability after testing intervals of two months
(r=.74) (Fischer & Turner, 1970). Test-retest reliability on each of the four subscales
ranged from r = .62 to r =.74 and the overall reliability of the scale was r = .83 (Fischer
& Turner, 1970). The internal consistency of each factored subscale was reported as
follows: Factor I (need), r = .67; Factor II (stigma), r= .70; Factor III (openness), r = .62;

and Factor IV (confidence), r = .74 (Fischer & Turner, 1970). However, Fischer &
Turner (1970) recommended that the four subscales, noted above used to measure these
dimensions, should be interpreted with reference to the overall scale, rather than used as
separate measures. Researchers reported that while each factor was reasonably well
defined in all three samples tested, the subscales contain relatively few items (Fischer &
Turner, 1970). Therefore, researchers who use the ATSPPHS, use the total scale scores
rather than subscale scores when calculating internal reliability estimates (Fischer &
Turner, 1970). Researchers Rayan and Jaradat (2016) found the ATSPPHS scale had
Cronbach’s α= 0.82 for a sample of 519 Jordanian university students. The specific range
of reliability estimates value was not reported for this study. Leong, Kim, and Gupta
(2011) noted internal reliability to be α =.82 with sample of 134 undergraduate university
students. Royal and Thompson (2012) provided confirmation of internal consistency for
a sample of 540 Christians. This included Pearson reliability estimates ranging
between .77 and .81 and item reliability estimates stable at .98. The researchers tested the
instrument in relation to Egyptian Muslim students; the difference in cultures (Muslim
culture versus Western culture) might have contributed to such low internal consistency
scores. Such drastic difference in reports for internal consistency is alarming. However,
the instrument has been very recently used in a large number of studies which looked at
help-seeking for mental illness in the Western culture.
Validity of ATSPPHS. In searching the literature for information on the different
types of validity for the ATTSPPHS scale, there were only a few studies that addressed
the various types of validity (i.e., discriminant, construct, face, criterion validity). The

majority of articles assessed did not report validity with their sample sizes and population
samples were limited to the Asian American population. Thus, further implicating the
importance of using this scale to further assess validity and reliability measures for the
African American community.
The ATSPPHS was also used to validate the parent-rating scale adaptation of the
ATSPPHS for a sample of 58 parents. The construct validity of the ATPPHS-P was
supported by its high correlation with the ATSPPHS, r = .93, p < .05 (Triemstra, Niec,
Peer, & Christian-Brandt 2017). According to Royal and Thompson (2012) the
ATSPPHS scale has been reported to show structural validity and content validity. The
component analysis of residuals performed on a sample of 540 Christians indicated that
item quality measures were sound and that the rating scale quality was confirmed to be
also psychometrically sound (Royal & Thompson, 2012).
Stigma of Mental Illness
Stigma of mental illness is an independent variable that was measured using the
SSOMI (See Appendix G). Permission to use the SSOMI scale was not required by the
original authors (Tucker et al., 2013). This is a 10-item scale developed to measure the
belief that having a mental illness would threaten one’s self regard, self-satisfaction,
selfconfidence, and overall worth. The scale was developed by Tucker et al. (2013) to
parallel the Self-Stigma of Seeking Help Scale by replacing questions referencing
seeking psychological help with references to mental illness. This scale was used in two
samples. One sample consisted of college students who experiencing psychological

distress, and the second sample was composed of primary care patients with reported
histories of mental illness.
Participants who complete the questionnaire are asked to rate statements
according to how they might react if they were to have a mental illness. Sample
statements from the questionnaire include “If I had a mental illness, I would be less
satisfied with myself.” Items are rated on a Likert scale from 1 to 5 (i.e., Strongly
Disagree =1, Agree =2, Agree/Disagree Equally =3, Agree =4, Strongly Agree=5). Half
of the items must be reverse-scored (Items 2, 4, 5, 7, & 9) so that higher scores represent
greater self-stigma associated with mental illness.
Reliability of SSOMI. Tucker et al. (2013) found that the SSOMI demonstrated
good internal consistency with Cronbach’s alpha at .91 for both the sample of 217
college students and 324 community members. Wallin, Maathz, Parling, and Hursti
(2018) investigated the impact of help-seeking and self-stigma as it related to the
intention to seeking online versus face to face psychological treatment for 267 students
(1st sample) and 195 primary care patients (2nd sample). Results demonstrated good
reliability 𝛼 = .85 for the 1st sample and 𝛼 = .87 for the 2nd sample. In a sample size of
333 school counselors, results demonstrated internal consistency with Cronbach’s
alpha .93 (Mullen & Crowe, 2017). Crowe, Mullen, and Littewood (2018) assessed 102
patients attending an integrated care medical center to collect data on participants’ self-
stigma of mental illness, self-stigma of seeking help, and mental health literacy. Results
demonstrated marginal internal consistency with Cronbach’s alpha at .69. In a sample
size of 448 undergraduates, Lannin, Vogel, Brenner, and Tucker (2015) assessed the

stigma of mental illness, the stigma in seeking psychological help and its’ effect on self-
esteem and intentions to seek counseling. Results demonstrated internal consistency with
Cronbach’s alpha score at .93.
Validity of SSOMI. In the original study that assessed self-stigma of mental
illness and with seeking psychological help for a sample of 217 college students and 324
community member history of being diagnosed with a mental illness, convergent validity
of the SSOMI was demonstrated through its strong, positive correlation with the
modified Self-Stigma of Depression scale (r= .73, p< .001) (Tucker et al., 2013).
However, the authors did not specify the actual values for convergent validity.
Discriminant validity for the SSOMI comes from its small, negative correlation with self-
esteem (r = -.25, p < .001). When it comes to construct validity, the SSOMI explained
around four times the amount of variance in the public stigma of mental illness (16% vs.
4%) while the Self Stigma of Seeking Help (SSOSH) explained approximately four times
the amount variance in the public stigma of seeking help (24% vs. 6%; Tucker et al.,
2013). In addition, the SSOSH explained approximately 36% of the variance in attitudes
toward seeking help, whereas the SSOMI explained negligible variance in these attitudes
(Tucker et al., 2013). In researching for different types of validity found with the SSOMI
scale, there were a limited amount of studies that either used the SSOMI or assessed
various types of validity (i.e., discriminant, construct, face, criterion validity). Therefore,
this research study assessing the stigma of mental illness for African American college
students assessed the validity for sample of participants recruited for this study.

Data Analysis Plan
In order to carry out the data analysis for this study, I used the SPSS software.
Data was downloaded from SurveyMonkey and into an excel spreadsheet for visual
inspection of the data. Data was then transferred into SPSS software program in order to
prepare it for data analysis. Participants’ demographic information were coded (for
example, male =1, female = 2) for all demographic questions that participants answered.
A separate demographic coding table was kept with the legend of the notations and codes
(See Appendix D). A separate coding legend for the ATSPPHS scale was also used for
coding and scoring purposes (See Appendix H).
First, data was analyzed visually for completeness to ensure that no data was
missing for individual questions for each entry. Entries that were missing information
were separated and moved into a different spreadsheet. Entries with missing data were
excluded from the data analysis. Then, data entered into SPSS and included a mixture of
descriptive and inferential statistics. Descriptive statistics such as means, range of scores,
and standard deviations were computed for coded variables. Data was visually displayed
through the use of tables and charts (i.e., bar graph, scatter plot, line graph). The data was
then analyzed in order to support the following research questions and hypotheses:
Research Question
What are the predictive relationships between ethnic identity, stigmas against
mental illness, perceptions of mental illness, and attitudes towards seeking professional
help for a mental health issues among African American college students after
controlling for gender?

H0: Ethnic identity (scores on the Multigroup Ethnic Identity Measure), stigma
against mental illness (scores on Self-Stigma of Mental Illness), and perceptions of
mental illness (scores on the Attitudes to Mental Illness Questionnaire) are not
statistically significant predictors of attitudes toward help seeking for mental illness
(scores on the Attitudes Toward Seeking Professional Help Scale) of African American
college students attending a HBCU after controlling for gender.
Ha: Ethnic identity (scores on the Multigroup Ethnic Identity Measure), stigma
against mental illness (scores on the SSOMI), and perceptions of mental illness (scores
on the Attitudes to Mental Illness Questionnaire) are - statistically significant predictors
of attitudes toward help seeking for mental illness (scores on the ATSPPHS) of African
American college students attending an HBCU after controlling for gender.
In order to test the null hypothesis, I used a multiple regression analysis. Multiple
regression was useful in this study because there were three independent variables (i.e.,
Ethnic identity, stigma against mental illness, perception of mental illness) that were
expected to predict a single dependent variable (Lalwani et al., 2013). Multiple
regression analysis is an example of statistical modeling that provides insight into the
conditional expectation about the ways that the dependent variable changes when values
of independent/predictor variables change (Lalwani et al., 2013; Rudestam & Newton,
2007).
Testing Statistical Assumptions
Before actually performing the multiple regression analysis, the key assumptions
for multiple linear regression were tested. Key assumptions to be tested included the

adequacy of sample size, multivariate normality, linear relationship between variables of
interest, absence of multicollinearity, and homoscedasticity. Details regarding how each
assumption was tested is presented below.
• Sample size: When it comes to the adequacy of the sample size, the sample size
was representative of the population (which was accounted for during the
planning and recruitment of the participants). The G*Power analysis was used
to determine the actual sample used in this study. In G*Power, the total
sample size is the number of participants summed over all groups of the
design (Faul et al., 2009).
●Normality: Multivariate normality occurs when each variable under
consideration are normally distributed with respect to each other variable
(Garson & Statistics Associates Publishing, 2012). There are a variety of
procedures that can be used to test for multivariate normality. For the purpose
of this study, the normality was assessed using a histogram. Normally
distributed variables are ideal when conducting a multi linear regression
analysis. However, non-normally distributed variables can distort
relationships and significant tests (Osborne & Waters, 2002). Researchers can
use visual inspection of data plots, skew, kurtosis, and P-P plots for
information about the normality of the variables as well as the
KolmogorovSmirnov tests which provides inferential statistics on normality
(Garson &

Statistics Associates Publishing, 2012; Osborne & Waters, 2002; Statistics
Solutions, 2018). This assumption was checked by using a histogram. The
histogram is a graphical method used to show evidence of normality of all the
variables. Histograms with the shape of a bell curve contain data in the set
that is normally distributed. The histogram can be used to check whether
residuals are not normally distributed (Statistical Solutions, 2018).
●Linearity: Multiple linear regression requires the relationship between the
independent and dependent variables to be linear (Statistics Solutions, 2018).
If the relationship between independent variables and the dependent variable
is not linear, the results of the regression analysis will under-estimate the true
relationship (Osborne & Waters, 2002). This can lead to an increased chance
of a Type II error for the independent variable and an increased risk of Type I
error for other independent variables that share variances with that IV
(Osborne & Waters, 2002). Scatterplots were used to test this assumption for
the purpose of this study. Scatterplots can show whether there are a
curvilinear and linear relationships (Statistical Solutions, 2018). A scatterplot
shows a linear relationship between X and Y exists when the pattern of X- and
Y- values appear as a line also, indicated as an uphill or downhill slope
(Statistical Solutions, 2018).
●Lack of multicollinearity: Another key assumption is little or no
multicollinearity. Multiple regression assumes that the independent variables
are not highly correlated with each other (Statistics Solutions, 2018).

Multicollinearity may be checked in multiple ways such as the correlation
matrix or variance inflation factor (VIF). For this study, the VIF was used.
The VIF of the linear regression indicates the degree that the variances in the
regression estimates are increased due to multicollinearity (Statistics
Solutions, 2018). The VIF was used to identify the variables causing
multicollinearity issues and removing those variables (Statistics Solutions,
2018). A correlations matrix can also be conducted to assess magnitude of the
relationships between the independent variables (i.e., ethnic identity, stigma
against mental illness and perceptions of mental illness) to ensure that there is
not a high degree of correlations among variables.
●Homoscedasticity: Homoscedasticity refers to where residuals are equally
distributed, whether they bunch together at some values or spread far apart
(Statistics Solutions, 2018). If the data is widely spread out, regression is not
going to work well (Statistics How To, 2015). The data for each of the
variables will be homoscedastic meaning that the variable of error is constant
(Casson & Farmer, 2014). The data will be randomly distributed by plotting
predicted values and residuals on a scatterplot (Statistics Solutions, 2018).
This assumption can be checked by visual examination of a plot of the
standardized residuals by the regression standardized predicted value using
SPSS (Osborne & Waters, 2002). In using a visual examination of a plot, only
clear patterns of the distribution are shown. The data is considered
heteroscedastic if a cone shaped pattern is shown on the plot (Statistics

Solutions, 2018).
Prescreening Data
1. Missing data: When it comes to prescreening my data for accuracy and
completeness there are steps that were taken to assess for missing data, outliers
and reliability analysis of the scales used in this study. Inaccurate inferences
about the data can be drawn if missing values are not handled properly by the
researcher (Statistics Solutions, 2018). There are two forms of randomly missing
values known as missing completely at random (MCAR) and missing at random
(MAR). MCAR exists when missing values are randomly distributed across all
observations and in MAR, missing values are not randomly distributed across
observations but are distributed within one or more sub-samples. In addition,
content analysis in SPSS was used to screen reverse coding errors and frequencies
of descriptive statistics and to detect missing values. A frequency chart is another
method that was utilized to determine whether there are missing values in the
data.
2. Outliers: Outliers can alter the outcome of the analysis and also violate normality
of the data collected (Garson & Statistical Associates Publishing, 2012). They are
abnormally distant values from most other values in your dataset. Outliers can be
caused by several different reasons that include errors of data entry, not defining
missing values, unintended sampling, separate models, missing at random data
and true non-normal distribution of data (Garson & Statistical Associates
Publishing, 2012). Outliers were visually assessed through the use of boxplots

and frequency charts. These outliers can also be examined for data entry or
measurement errors. Outliers are dropped when appropriate if there are errors of
data entry, missing values that are not defined, unintended sampling, separate
models, omitted data are missing at random and for true non-normal distributions
with extreme values (Garson & Statistical Associates Publishing, 2012).
3. Reliability Analysis of the scales to be used. For the purpose of testing for
internal consistency of instruments that were used in this study, Cronbach’s alpha
test was used. When using Likert-type scales it is imperative to calculate and
report
Cronbach’s alpha coefficient for internal consistency reliability for any scales or
subscales one may be using (Gliem & Gliem, 2003). Cronbach’s alpha is a test
reliability technique that requires only a single test administration to provide a
unique estimate of the reliability for a given test (Gliem & Gliem, 2003). The
Cronbach’s α result is a number between 0 and 1 and an acceptable reliability
score is one that is 0.7 and higher (Heale, & Twycross, 2015). I conducted and
reported a reliability analysis for each instrument used to collect data for this
study.
Threats to Validity
As with some studies, there are threats to internal, external validity and threats to
statistical conclusion in this study that will be addressed. The first section will address
threats to internal validity. Internal validity refers to whether the effects observed in a
study are due to the manipulation of the independent variable and not some other factor

(Onwuegbuzie, 2000). The second section will discuss threats to external validity.
External validity refers to how well the results of the stud can be generalized. And, lastly,
statistical conclusion validity will also be discussed.
Threats to Internal Validity
Some threats to internal validity in this study included the presence of
confounding variables. Internal validity is achieved by ensuring that confounding
variables have been controlled (Garcia-Perez, 2012). A confounding variable is an
extraneous variable that influences the dependent variable or independent variable
(Khorsan & Crawford, 2014). Avoiding or having a lower number of confounding
variables results in high internal validity (Statistics How To, 2015).
Further, these aspects of their lives were expected to be ordinary and were not
expected to create a large effect on participants’ answers. No history effects were
expected to affect the results of the study, because the study is not longitudinal and it was
anticipated to only take a small fraction of participants’ day to complete (Creswell, 2014;
Onwuegbuzie, 2000). In addition, the study is a cross-sectional design whereby data was
only to be collected once. Maturation effects are also not expected to affect the results of
the study, since no normal processes with expected maturation are expected to take place
during the study, such as fatigue, for example (Creswell, 2014; Onwuegbuzie, 2000). The
questionnaires were not expected to take participants a long time. The type of sampling
selected for this study was also not expected to have an effect since participants were not
broken down into various groups (Creswell, 2014; Khorsan & Crawford, 2014;
Onwuegbuzie, 2000).

Threats to External Validity
Threats to external validity included the representativeness of the sample in the
study. In this case, a convenience sample and snowball sampling were used. This study
used anyone as participant who responded to the recruitment emails and flyers. Existing
participants also recruited participants as future subjects to participate in the study.
Therefore, results were interpreted with the idea of possible threats to representativeness
of the sample. Another possible threat was the reactive effect of testing in this case, the
scale/instrument that subjects complete first may influence their choices in answers on
consequent scales (Onwuegbuzie, 2000). Because I did not have direct communication
with the participants, there was no way to ensure that the questionnaires might be filled
in random order by different participants. Therefore, questionnaires were interpreted with
the knowledge that the reactive effect of testing might influence the results.
Threats to Statistical Conclusion Validity
Statistical conclusion validity holds when the conclusions of a research study are
founded on an adequate analysis of the data (Garcia-Perez, 2012). Statistical conclusion
validity pertains to the extent that data reveals a link or lack of association between
independent and dependent variables (Garcia-Perez, 2012). There are threats to statistical
conclusion validity that could lead to making incorrect conclusions about relationships.
For example, threats may include fishing, low statistical power, random irrelevancies in
the setting, unreliable measures, and violated assumptions for tests. Fishing results when
tests are repeated in order to find something significant which can result in incorrectly
concluding that there is a relationship when there is not. Low statistical power can lead to

concluding that there is no relationship between variables (Statistics How To, 2015).
Random irrelevancies in the setting refer to any distractions that participants may
experience in their setting while completing the study. Unreliable measures refer to over
or underestimating the size of the relationship between variables. Violated assumptions
for tests can lead to underestimating or overestimating effects.
In order to improve conclusion validity, using a larger sample study when
possible can impact the statistical power. The general rule of thumb in research is for
statistical power to be at 0.8 in order to find a relationship when there is one (Trochim,
2006). Increasing the risk of making a Type 1 error by raising the alpha level (i.e. 0.05
significance level to 0.10) can help reduce threat to statistical conclusion validity. In
addition, conclusion validity can be improved by assuring good implementation,
increasing number of questions on a scale when possible or by reducing situational
distractions in the measurement context (Trochim, 2006).
Ethical Procedures
In order to conduct a fully ethical study, ethical principles that the APA has set
forward were practiced. First, the study used the premise of informed consent, because it
is unethical to conduct a study on human subjects without their consent. Because college
students were the targeted population for the study, there was a small chance that some
of them could have been minors (less than 18 years old) when recruited for the study. All
participants were asked to give their age and date of birth on the demographic survey to
indicate whether they met the age requirement. In this case, only students of 18 years and
up were allowed to participate in the study. Any files of participants that did not meet

inclusion criteria were deleted. For subjects 18 years old and older, regular informed
consent forms were used. Informed consent forms previously approved by the IRB
committee (02-12-19-0350743) were identified on the informed consent form that were
accessible to subjects before they begin to participate in the survey. The screening survey
also assisted in qualifying participants who fully met requirements of the study (See
Appendix A). If participants did not meet the age, ethnicity, or HBCU requirement, then
they were not allowed to move forward with the study. The screening survey and the
demographic questionnaire served as barriers in disqualifying participants who did not
meet eligibility requirements. Next, instructions clearly directed participants to only
move forward with participation if they agreed with contents disclosed on the informed
consent form. Participants were advised by a message on the screen that moving forward
with the survey indicated consent to participate in the study. Participants were also given
the option to print a copy of the informed consent form if they desired to have a copy.
Ethical concerns related to recruitment materials include respect for subjects’
privacy, not putting pressure on subjects to participate in the study (respecting their need
to think about participation or refuse it altogether), describing the study to participants
clearly, simply, and accurately, without any biases and not asking for personally
identifiable information from participants (i.e., by not requesting first and last names or
date of birth information on surveys). Participants were informed that their privacy
would be protected by limiting access to obtaining and assessing data to the researcher
and keeping survey results received locked on a password protected computer. An
important ethical consideration related to collection of data was bias in the way that

questions were asked, which was negated by the fact that only already made, peer-
reviewed tools were used in the study.
Confidentiality was another important issue of consideration in this study.
Maintaining the privacy of sensitive information collected during the study is important.
Only aggregated data was reported in the findings. Any research related documents
printed were properly stored. All printed documents (i.e., participants’ questionnaires,
hard copies of data spreadsheets, and any other documents) related to the study were kept
in a locked file cabinet. All data was downloaded into secure files protected by
passwords. Only the researcher has the key to that lock.
Further, all electronic copies of any data related to the study were kept in a
separate folder on my computer. Aside from the fact that, the computer was protected by
a password, the folder has its own password that only the researcher has access to. Data
will be kept for the required amount of 5 years according to Walden University’s
protocol. After 5 years, any physical data will be burned, and an IT specialist will be
contacted to advise on how to delete data from my computer fully, because parts and
copies of files could be in multiple registries within the computer system at the end of the
allotted time period.
Summary
The purpose of this quantitative correlational study was to examine the predictive
relationships between ethnic identity, perceptions of mental illness, stigma of mental
illness and attitudes toward seeking professional help for mental illness among African
American college students attending HBCUs. This chapter provided a detailed

description of the research design that was used which is a quantitative, cross-sectional
research design. A detailed description of procedures for recruitment used was included.
Participants for this study were voluntary and recruited across institutions within the
Atlanta, GA area. Procedures further explained that participants would retrieve research
related documents online via SurveyMonkey for this survey research study. For sampling
procedures, participants were randomly selected for this study. This correlational study
of relationships between the independent and dependent variables used multiple
regression for statistical testing. Data analysis was completed through the use of SPSS
software.
Instrumentation included for the purpose of this study include the AMIQ, ATSPPHS,
SSOMI, and MEIM-R. Key assumptions tested were discussed and this included the
adequacy of sample size, multivariate normality, linear relationship between variables of
interest, no or little multicollinearity, homoscedasticity, and independence of errors.
Steps utilized to pre-screen data, avoid missing data, outliers and analyze reliability for
instruments used was included. In addition, a description of threats to validity, internal
validity, statistical conclusion validity and ethical considerations were discussed.
Chapter 4 provides the statistical analysis and a detailed statistical outcome of the
present study.
Chapter 4: Results

Introduction
The purpose of this quantitative study was to explore the predictive relationships
between ethnic identity, perceptions of mental illness, stigma against mental illness and
attitudes toward seeking professional help for mental illness among African American
college students attending HBCUs. The following research question was addressed:
What are the predictive relationships between ethnic identity, stigmas against mental
illness, perceptions of mental illness, and attitudes towards seeking professional help for
mental health issues among African American college students after controlling for
gender?
The following two hypotheses were tested using a multiple linear regression
analysis:
H0: Ethnic identity (scores on the Multigroup Ethnic Identity Measure), stigma
against mental illness (scores on Self Stigma of Mental Illness), and perceptions of
mental illness (scores on the Attitudes to Mental Illness Questionnaire) are statistically
significant predictors of attitudes toward help seeking for mental illness (scores on the
Attitudes Toward Seeking Professional Help Scale) of African American college students
attending an HBCU after controlling for gender.
Ha: Ethnic identity (scores on the Multigroup Ethnic Identity Measure), stigma
against mental illness (scores on Self Stigma of Mental Illness), and perceptions of
mental illness (scores on the Attitudes to Mental Illness Questionnaire) are not
statistically significant predictors of attitudes toward help seeking for mental illness

(scores on the Attitudes Toward Seeking Professional Help Scale) of African American
college students attending an HBCU after controlling for gender.
The purpose of this chapter is to review and discuss the statistical results
conducted for hypothesis testing. In this chapter, I present a review of the data collection
processes and procedures and continue with a discussion of the study participants. The
results section includes data analyses (e.g., descriptive statistics, testing of assumptions)
as well as results from the multiple linear regression. I conclude the chapter with a
summary of the results.
Data Collection
The data collection process began on April 9, 2019 and ended on August 8, 2019,
lasting over a period of approximately 17 weeks. I sought participants through social
media sites such as Facebook and Instagram. The post on Facebook was made public to
be viewable and open to share on any community, business, organization, or personal
page that an individual shared it to. A flyer that contained a brief description of the study,
basic eligibility criteria, link to complete the survey, and contact information was posted
on these social media sites (Facebook and Instagram). In addition, participants were
recruited via all three Atlanta universities: Spelman College, Clark, Atlanta University,
and Morehouse College via email broadcast and flyer postings. Spelman College and
Clark Atlanta University required me to obtain a sponsored faculty member in order to
complete data collection on their campus. This approval was required before proceeding
with the application for each institution’s IRB approval.

All data were collected via an online survey platform called SurveyMonkey.
Participants were required to complete a screening survey (see Appendix A) and
demographic questionnaire (see Appendix C) to ensure that each participant met
qualifications to participate in the study. Participants then completed the SSOMI,
MEIMR, ATSPPHS, and the AMIQ. The survey took approximately 15 minutes to
complete.
There were minor discrepancies that arose in the data collection process from the
plan presented in Chapter 3. Although IRB approval was obtained from both Morehouse
and Spelman College early on, the recruitment of college students from each campus
took longer than expected. A change of procedures form was submitted to allow the
process to move forward without Clark Atlanta University approval due to a lack of
communication from the university.
In addition, the approval of a second change of procedures form was requested to
Walden University IRB department in order to ensure that a sufficient number of college
students could be recruited for this study and to adjust the length of time the online
survey took to complete from 30 minutes to 15 minutes. Because there was a delay in
obtaining a research sponsored faculty member and IRB approval from Clark Atlanta
University, a request to include snowballing sampling was also requested to further
expedite the process. There was limited access to recruiting students on campus due to
the college semester at each of the Atlanta University campuses coming to an end at the
end of April 2019. This resulted in a slow response rate, and, for this reason, convenience
sampling and snowball sampling were used once approved. In addition, a limited number

of Morehouse students participated in this study, and this may have been due to a delay
with the school’s communication department sending an email broadcast to all
Morehouse College students for participation in the study. This delay continued until
after the Spring semester ended. The bulk of data collected from participants occurred
towards the latter 3 weeks of the data collection.
A total of 85 participants completed the research study. All qualified participants
were African American college students between 18 and 23 years of age who attended
either Spelman College, Morehouse College, or Clark Atlanta University. A screening
survey was used to further assist in qualifying individuals appropriate for the study (see
Appendix A). The screening survey consisted of the following three questions: (a) Are
you currently between the ages of 18 and 23? (b) Do you currently attend Morehouse
College, Spelman College, or Clark Atlanta University? and (c) With which racial or
ethnic category do you primarily identify? Participants who did not meet qualifications
were thanked for their willingness to participate and exited from the survey. Participants
who did meet survey qualifications completed the demographic questionnaire, which
served as another barrier to eliminate students who did not qualify for this research study.
All of the data were then downloaded from SurveyMonkey and into an Excel spreadsheet
so that I could visually inspect the data for missing data and outliers. Data were then
coded for subsequent analysis using SPSS.
Results

Descriptive Statistics of Demographic Variables
Descriptive statistics were used to examine demographic variables. In the
descriptive statistics, measurements for central tendency and varied data values for
demographic variables such as (a) frequencies, (b) mean, (c) standard deviation, and (d)
ranges were assessed. Table 2 presents a summary of results for the demographic data.
The data showed that a majority of students (22%) were of age 19. For gender, there
were
65 (76%) females and 20 (24%) males. The data revealed that 27 (32%) participants were
Sophomores. When it came to the number of students at each HBCU, most of the
respondents N = 44 were from Spelman College and 63 (74%) were identified as being
in an undergraduate degree program.
Table 2
Descriptive Statistics of Demographic Variables
Variable Frequency Percent
Age 18
13 15.3
19 19 22.4
20 20 23.5
21 13 15.3
22 10 11.8
23 10 11.8
Gender
Female 65 76.5
Male 20 23.5
Academic classification
Freshman 15 17.6
Sophomore 27 31.8
Junior 21 24.7
Senior 21 24.7

Other 1 1.2
School currently attendi
Spelman College
ng
44 51.8
Morehouse College 12 14.1
Clark Atlanta
University
29 34.1
Degree program
Undergraduate
Degree program
63 74.1
Graduate Degree
Program
22 25.9
Descriptive Statistics of Independent and Dependent Variables
The three independent variables in this study were scores on the MEIM-R, the
SSOMI, and the AMIQ. The dependent variable for this study was the ATSPPHS. A
summary of the descriptive statistics for each instrument is presented in Table 3. Table 3
presents data for the total scores for both the independent and dependent variables used
in this study. The MEIM-R instrument measured how well an individual relates to a
certain ethnic identity group (M = 23.60, SD = 5.09). The AMIQ instrument measured
one’s perception towards an individual diagnosed with a mental illness (M= -2.15, SD =
3.38). The SSOMI measured whether the belief that having a mental illness would
threaten one’s self regard, self-satisfaction, self-confidence, and overall worth (M=
30.85, SD = 7.01). The ATSPPHS instrument was used to assess attitudes toward and
willingness to seek treatment for mental illness from a professional mental health
provider. Overall, participants averaged in the lower range of scores (M = 49.98, SD =
11.98). However, Fischer and Turner (1970) recommended that the four subscales be
analyzed with reference to the overall scale rather than as separate measures. The

ATSPPHS instrument scores have negative attitude toward and willingness to seek
mental health treatment from a professional mental health provider (M = 49.98, SD =
11.98).
Table 3
Descriptive Statistics of IV’s and DV for Total Sample
Ethnic identity 85 24.00 6.00 30.00 23.60 5.09
Attitudes toward
seeking help for
mental illness
85 50.00 28.00 78.00 49.98 11.98
Attitudes toward
mental illness
85 18 -10 8 -2.15 3.38
stigma against mental
illness
85 34 16 50 30.85 7.01
Valid N (listwise)
85
Std.
N Range Minimum Maximum Mean
Deviation Prescreening of the Data
Before evaluating the statistical assumptions for this study, I prescreened the
data for accuracy and completeness of all data collected. I assessed for missing data,
outliers, and the reliability data collected by the instruments used in this study. One
of the tools used to examine missing data was managed through a visual assessment
of the data and content analysis in SPSS. Data entries were visually checked by
administering a frequency count for every variable using a Microsoft Excel
spreadsheet. Subsequently, no missing data were found from all 85 responses

collected. The online survey was also set up to not allow participants to move
forward in answering questions without giving a response to each question asked.
Outliers were assessed through the use of a box plot and frequency charts.
Testing Statistical Assumptions
In the following section, I tested key assumptions for multiple linear
regression. The hypotheses stated for the purpose of this study were examined using a
regression analysis. Key assumptions tested in this study included adequacy of sample
size, multivariate normality, linear relationship between variables of interest, absence
of multicollinearity, and homoscedasticity.
Sample size. Based on a power analysis via G*Power, for a multiple linear
regression analysis, a medium effect size (ƒ²) of .15, three predictor variables, power
set at .80, and an alpha level of .05, the required sample size for this study was N
=77. The actual sample size of the study was N = 85. All 85 participants completed
100% of the survey which indicates that the sample size was adequate.
Normality. A histogram was utilized to determine whether the data collected
on the dependent variable was normally distributed. As presented, the data
approximated the overall shape of a normal distribution of scores. This was evidenced
by the display of a bell-shaped curve. Therefore, I concluded that the data for
ATSPPHS scores were approximately normally distributed as indicated by the graph
displayed in Figure 1.
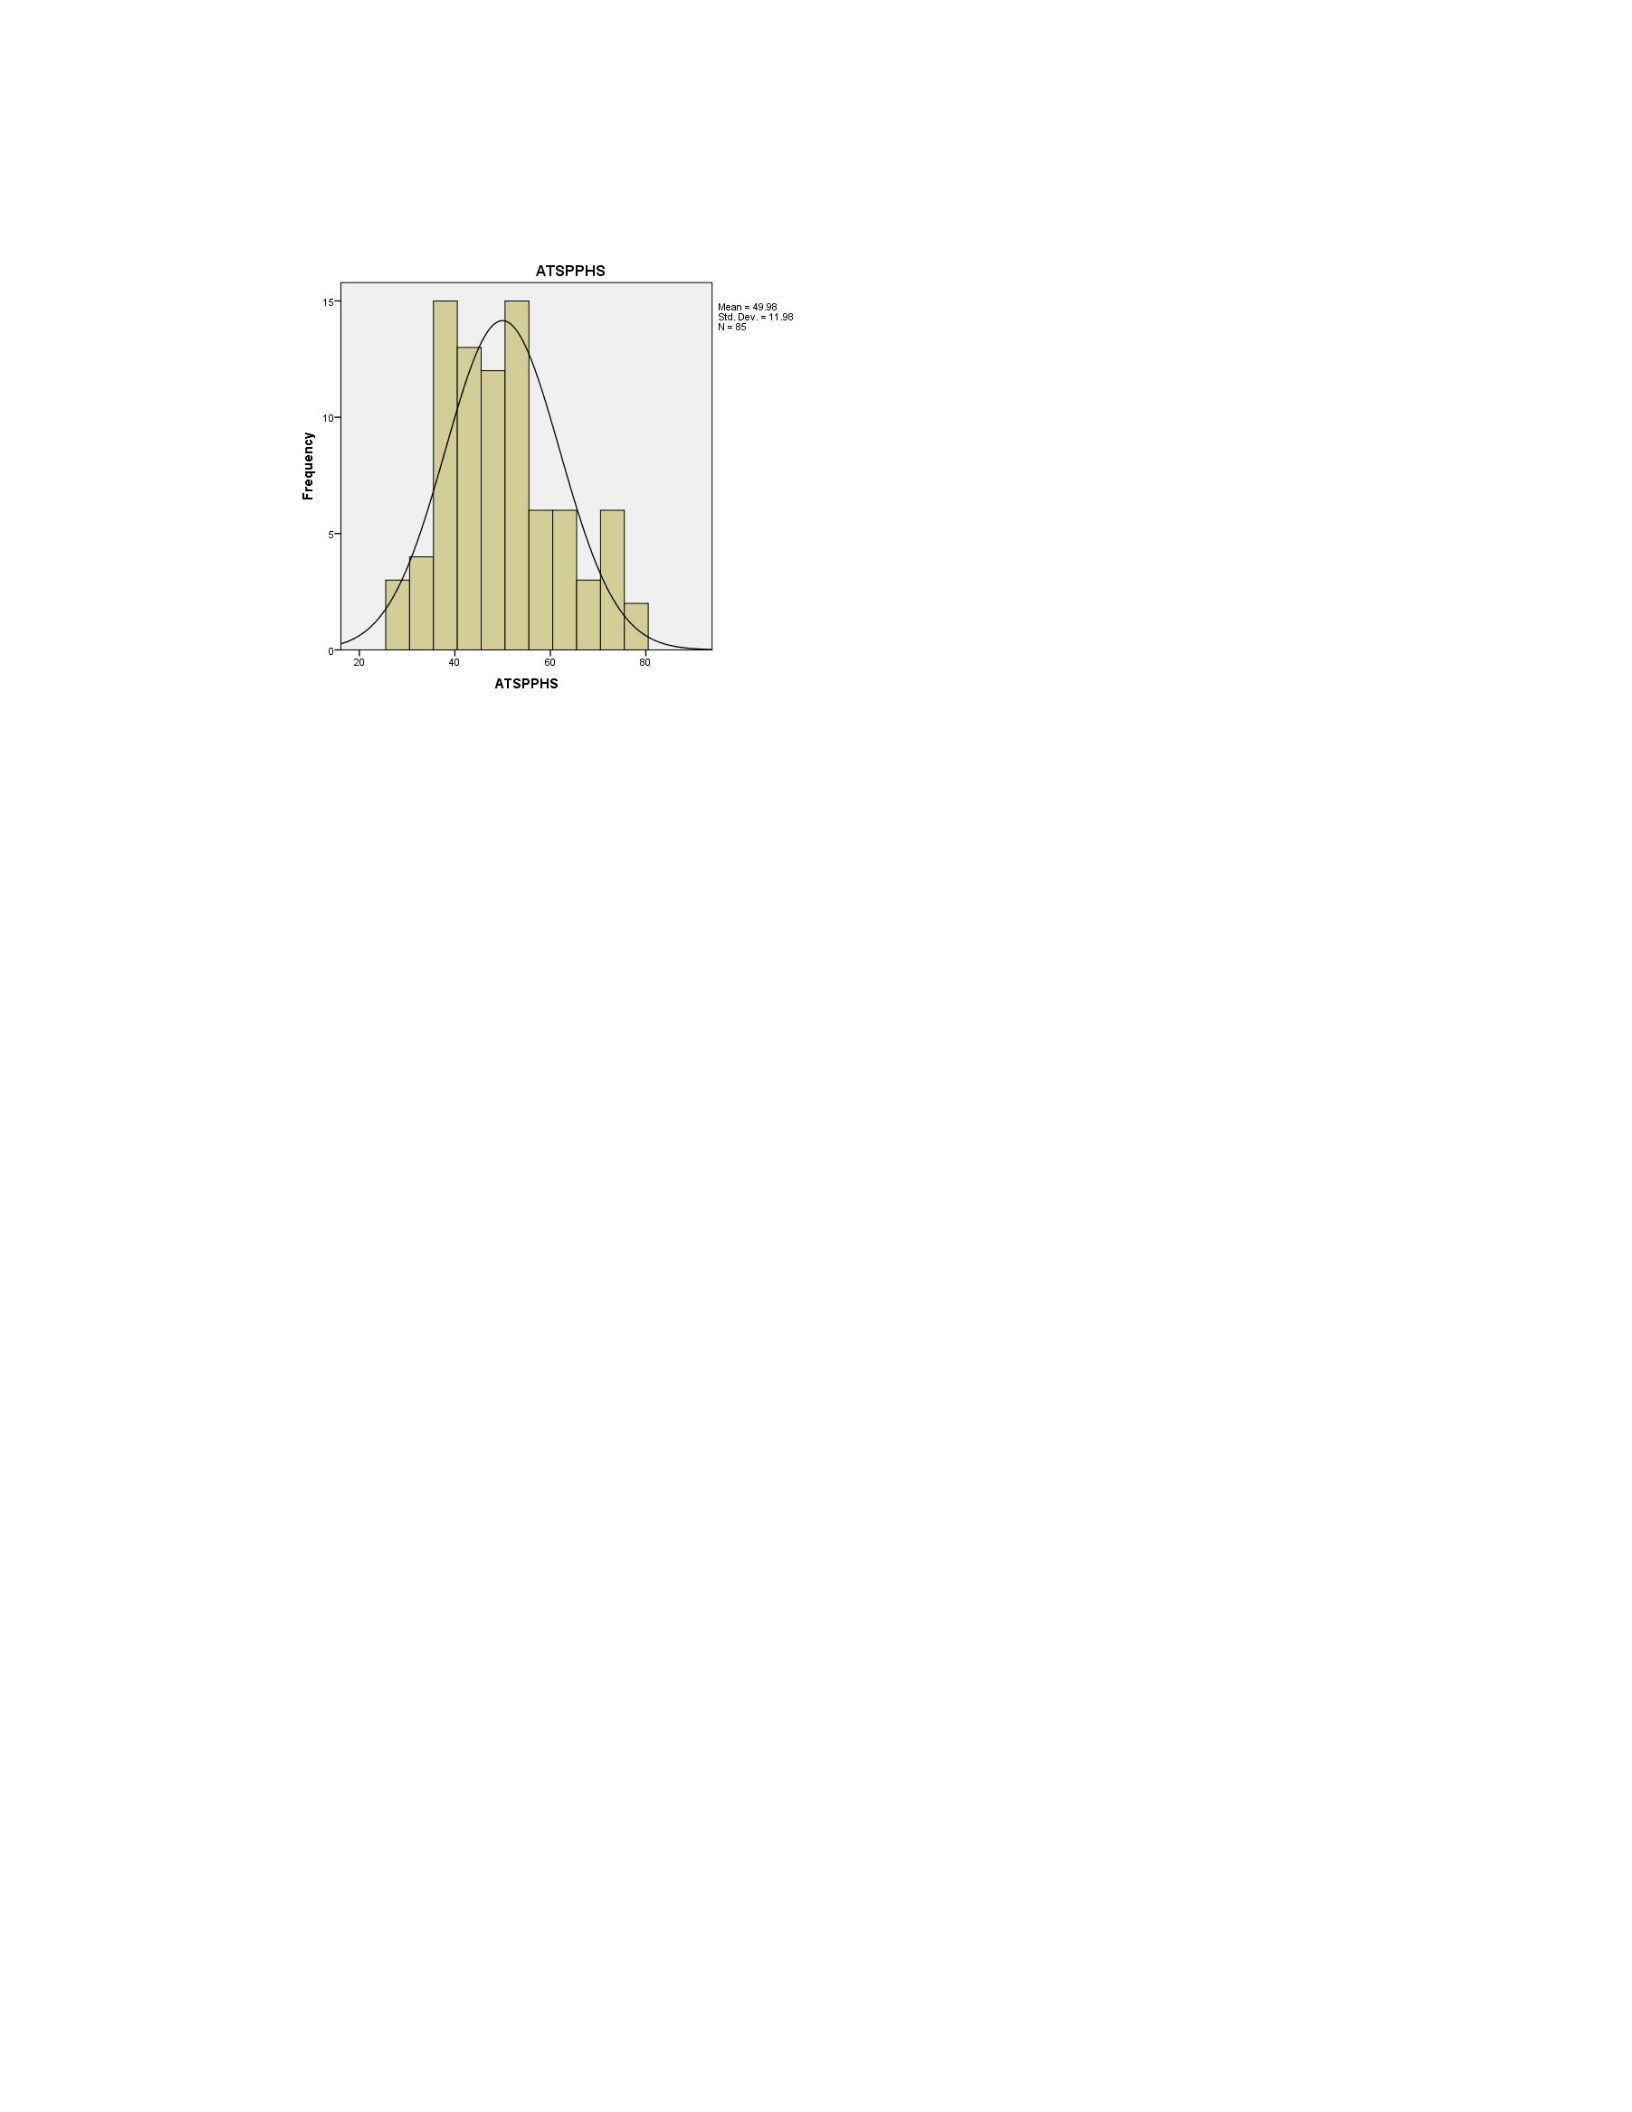
Figure 1. Histogram for ATSPPHS.
Linearity. Scatterplots were used to test the linearity assumption. The use of
a scatterplot graph provides a visual representation of relationship between variables.
The scatterplot of standardized predicted values showed that the data met the
assumptions of linearity. Each graph showed a straight line of fit indicating
assumption of linearity has been met (See Figure 2, 3, 4, 5). Although the
assumption of linearity was met the correlation was weak. A correlation coefficient
was further evaluated to assess relationship between the independent and dependent
variables. A correlation coefficient is an index that describes the relationship and can
take on values between −1.0 and +1.0, with a positive correlation coefficient
indicating a positive correlation and a negative correlation coefficient indicating a
negative correlation (CK12, 2016). Based on the results obtained from the
correlation analysis in table 4 it can be observed that there is no significant
correlation between the variables ETHNIC IDENTITY, SSOMI, AMIQ, and
ATSPPHS. However, according to table 4, the gender variable and the dependent
variable
(ATSPPHS) showed a significant relationship r=-.28, p=.01.
Table 4
Correlation Table
MEIM-
R AMIQ SSOMI
ATSPP
HS Gender
ETHNIC
IDENTITY
Pearson
Correlation
1.00 .15 -.02 .03 .08
Sig. (2-tailed) .16 .86 .78 .48
N 85.00 85.00 85.00 85.00 85.00
Attitudes
Toward Mental
Illness
Pearson
Correlation
.15 1.00 -.28** .01 .10
Sig. (2-tailed) .16 .01 .89 .36
N 85.00 85.00 85.00 85.00 85.00
Self-Stigma of
Mental Illness
Pearson
Correlation
-.02 -.28** 1.00 -.02 -.16
Sig. (2-tailed) .86 .01 .88 .15
N 85.00 85.00 85.00 85.00 85.00
Attitudes Pearson
Toward Seeking Correlation
.03 .01 -.02 1.00 -.28**
Help for Mental Sig. (2-tailed) .78 .89 .88 .01
Illness N 85.00 85.00 85.00 85.00 85.00
Gender? Pearson
Correlation
.08 .10 -.16 -.28** 1.00
Sig. (2-tailed) .48 .36 .15 .01
N 85.00 85.00 85.00 85.00 85.00
**. Correlation is significant at the 0.01 level (2-tailed).
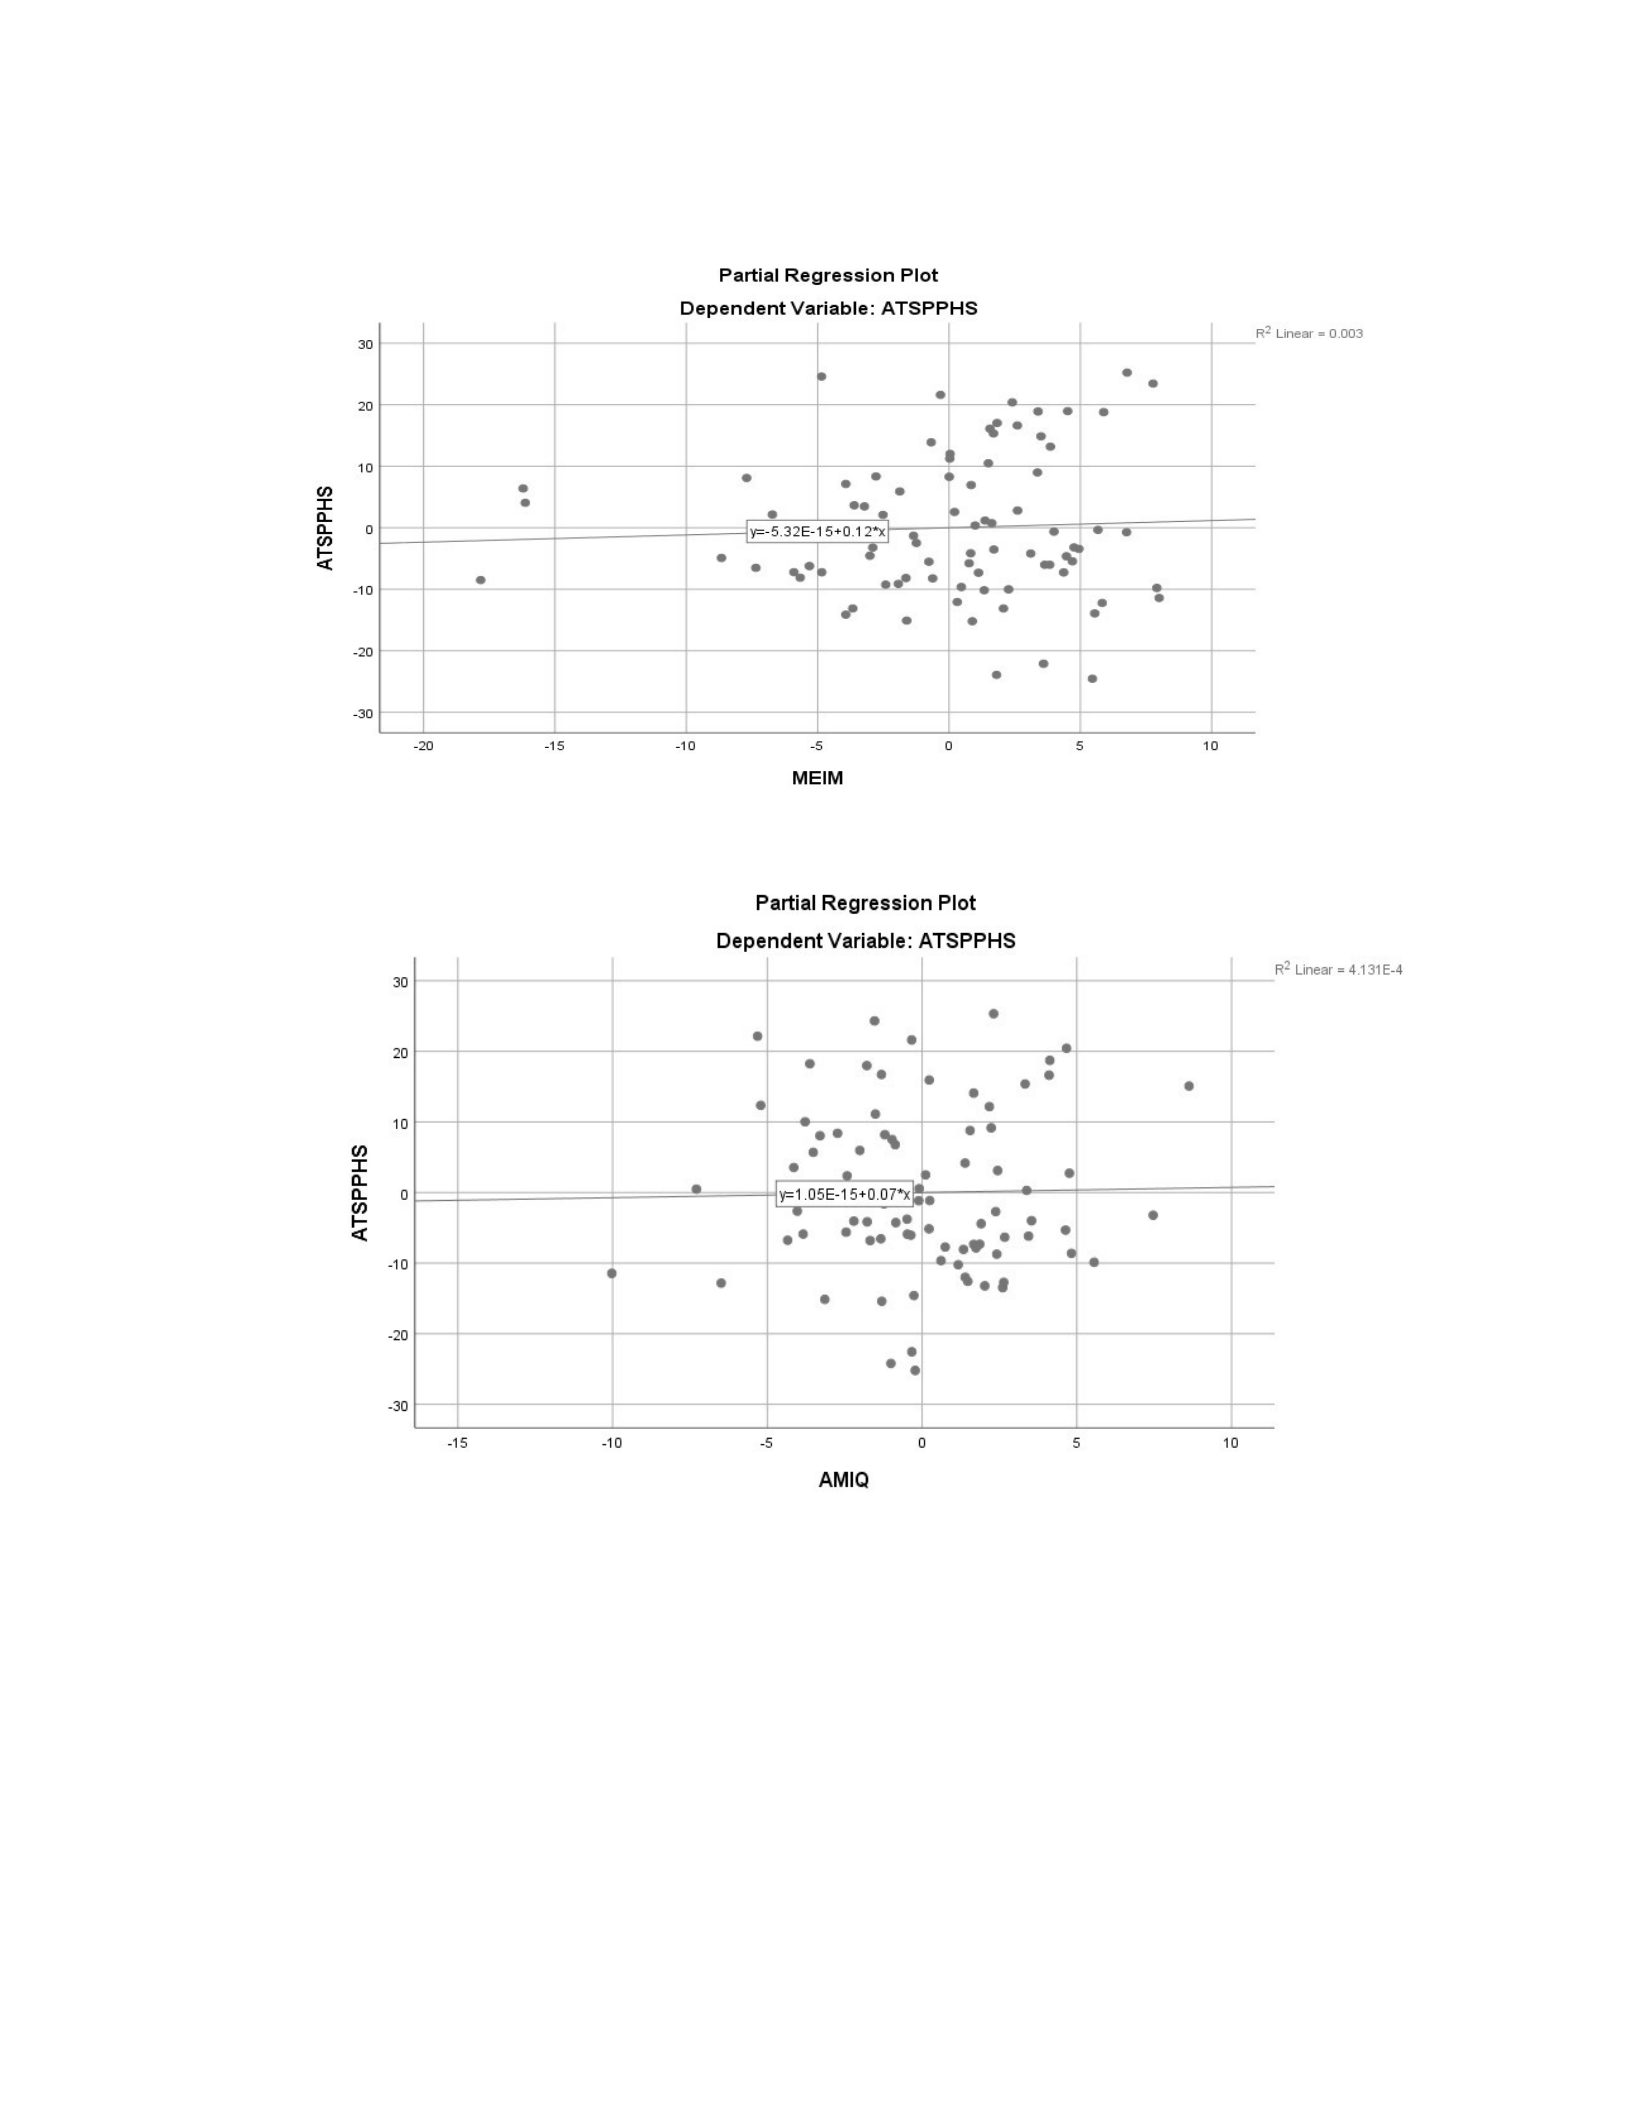
Figure 2. Scatterplot for DV ATSPPHS and IV ethnic identity (MEIM-R).
Figure 3. Scatterplot for DV ATSPPHS and IV AMIQ.
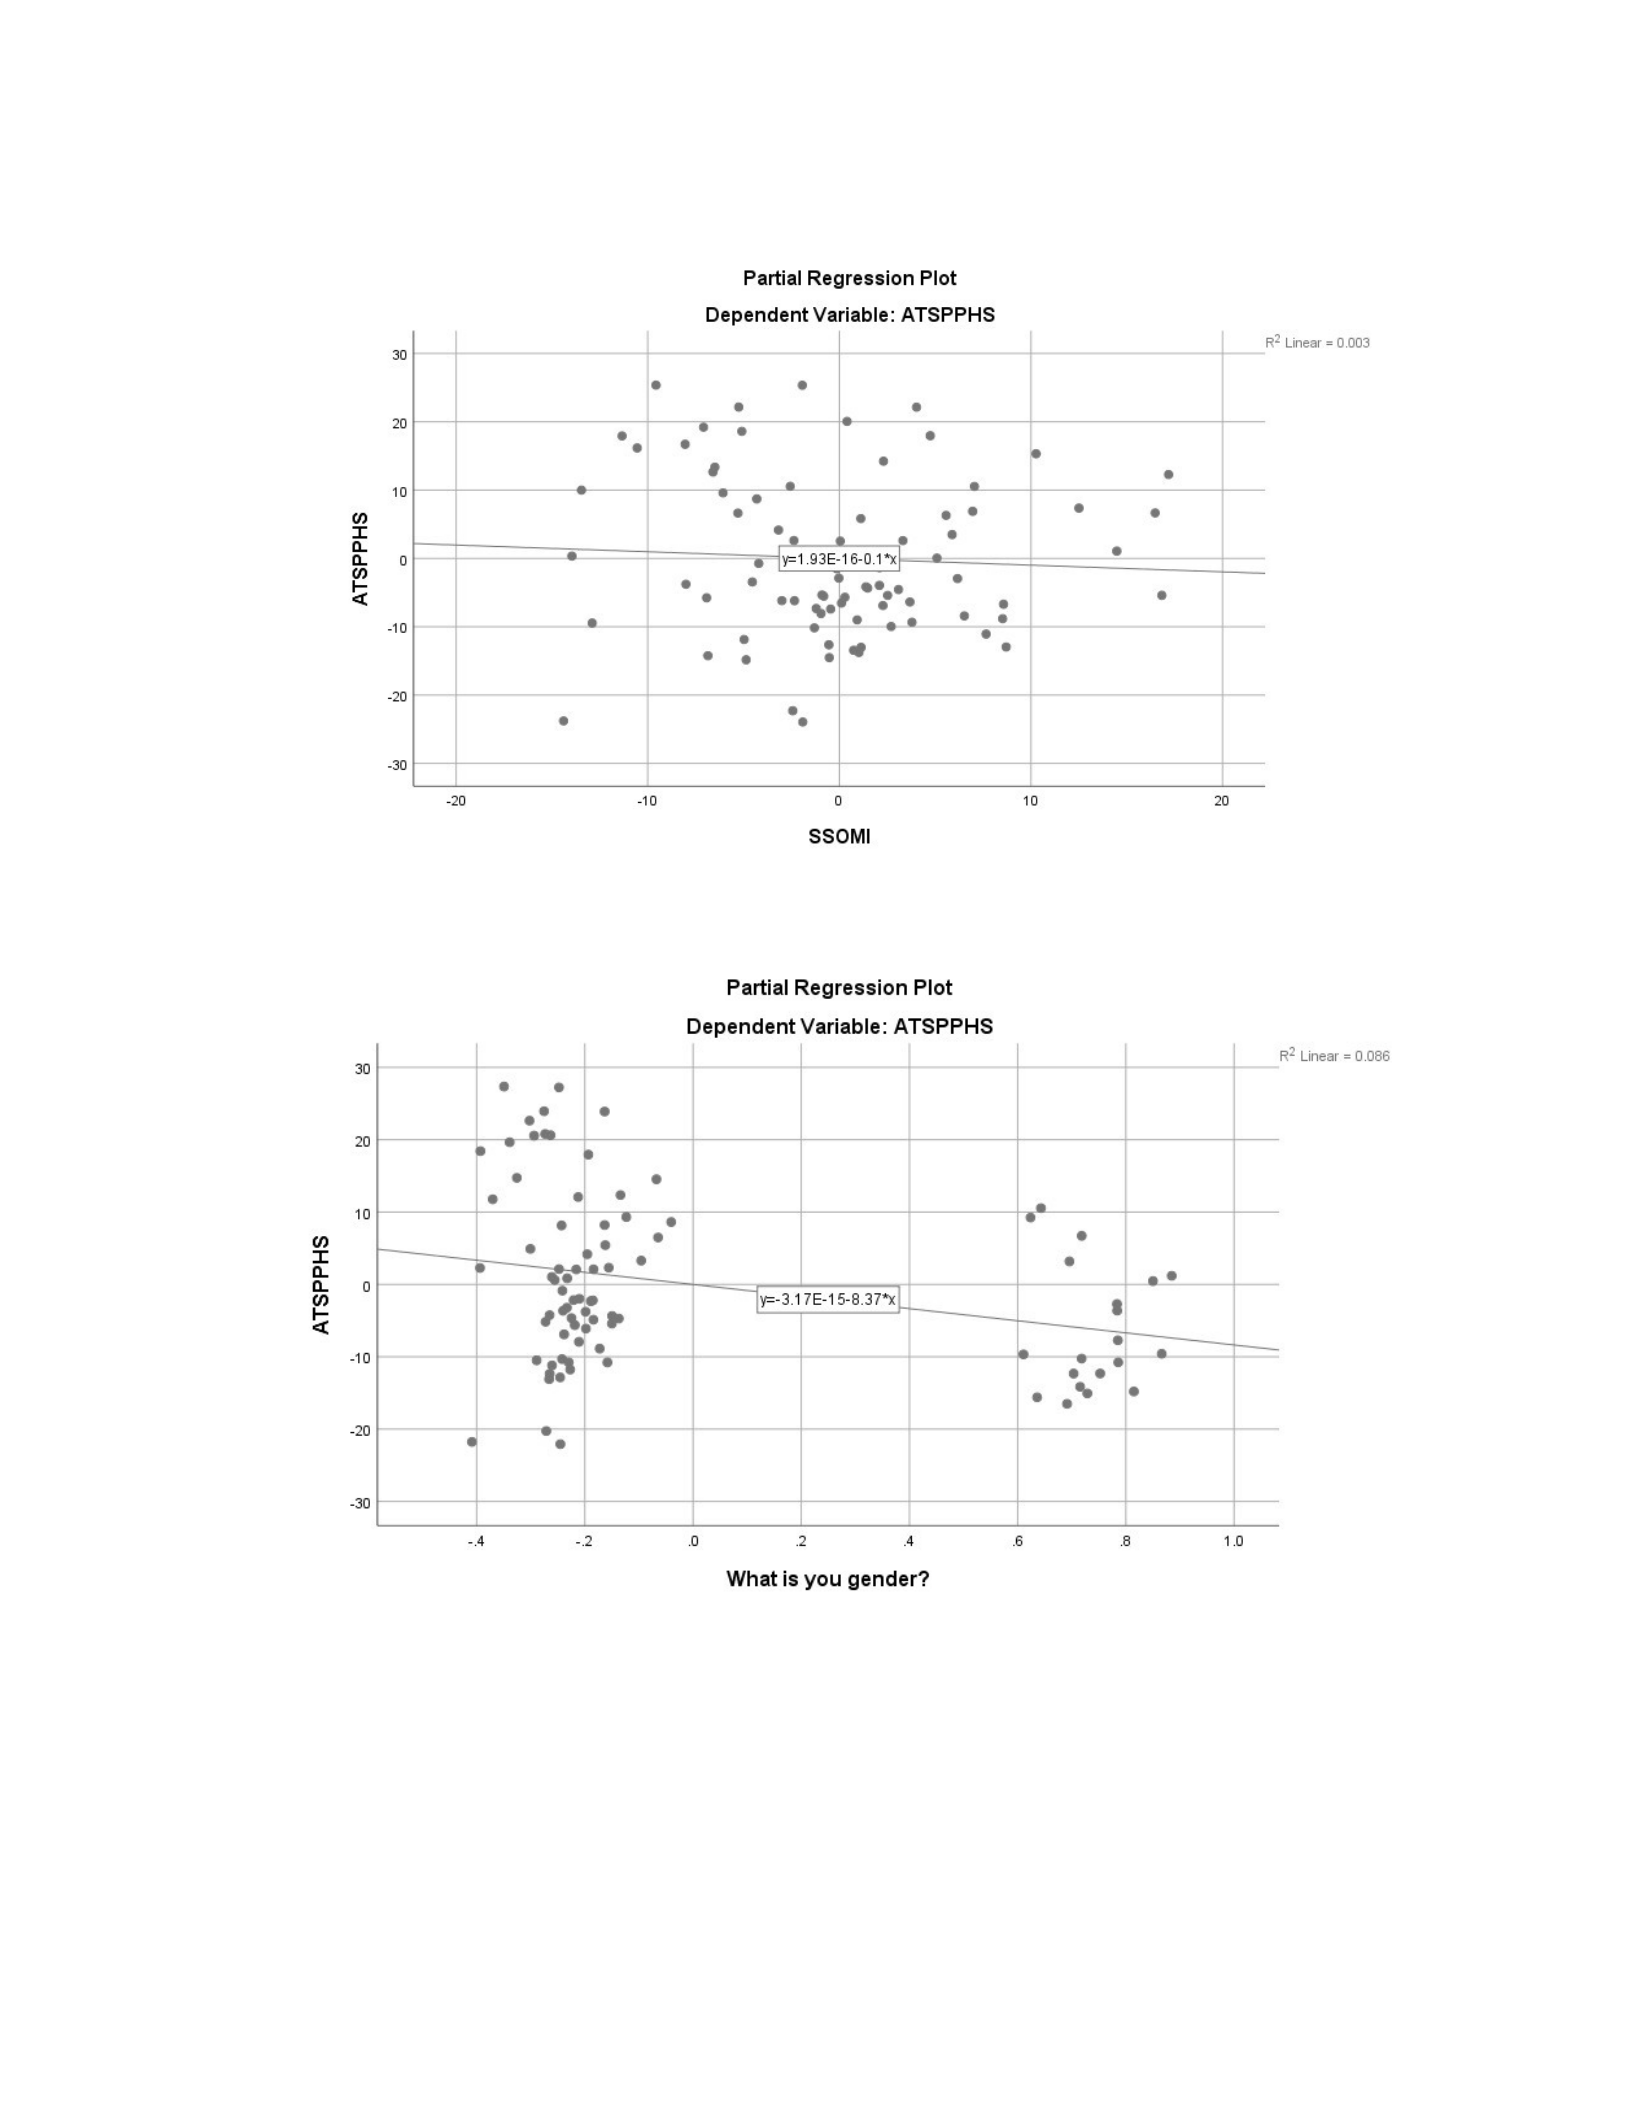
Figure 4. Scatterplot for DV ATSPPHS and IV SSOMI.
Figure 5. Scatterplot for DV ATSPPHS and IV gender.
Lack of multicollinearity. Multicollinearity is a state of high intercorrelations
among the independent variables (Statistic Solutions, 2018). In order to test for a lack of

multicollinearity, the Variance Inflation Factor (VIF) was utilized. The VIF
identifies correlation between independent variables and the strength of that correlation
(Statistics Solutions, 2018). If the value of tolerance is less than .2 and the value of VIF
is 10 and above, then the multicollinearity is considered to be problematic (Statistics
Solutions, 2018). To meet this assumption, the VIF value should remain between .2 and
10. In our case, all variables in both models showed that there were no statistically
significant correlations between the three independent variables as the VIF value were
between .2 and 10. A review of the data in Table 5 reveals that all VIF values were
less than 10. The general rule of thumb is that values greater than .2 indicate a lack
of multicollinearity among the variables (Stephens, 2009). Based on the obtained
VIF and tolerance values presented, the assumption regarding the lack of
multicollinearity was met for the data collected in this study.
Table 5
Collinearity Statistics
Model IVs Tolerance VIF
Model 1 Ethnic
Identity
.98 1.03
Attitudes to
Mental Illness
Questionnaire
.90 1.11

Model 2
Self-Stigma
of Mental Illness
.92 1.09
Ethnic
Identity
.97 1.03
Attitudes to
Mental Illness
Questionnaire
.90 1.12
Self-Stigma
of Mental Illness
.90 1.11
Gender? .96 1.03
Homoscedasticity. When checking for homoscedasticity, the variance around the
regression line is the same for all values of the predictor variable. When the variable of
error is constant, the data for each variable is considered to be homoscedastic (Casson &
Farmer, 2014). When the homoscedasticity assumption is met, residuals will form a
pattern less cloud of dots (Garson, 2012). As shown in the scatterplots in figures 6, 7,
8, and 9, a visual examination of the dots shows a clear pattern of the distribution.
This fulfills the homoscedasticity assumption.
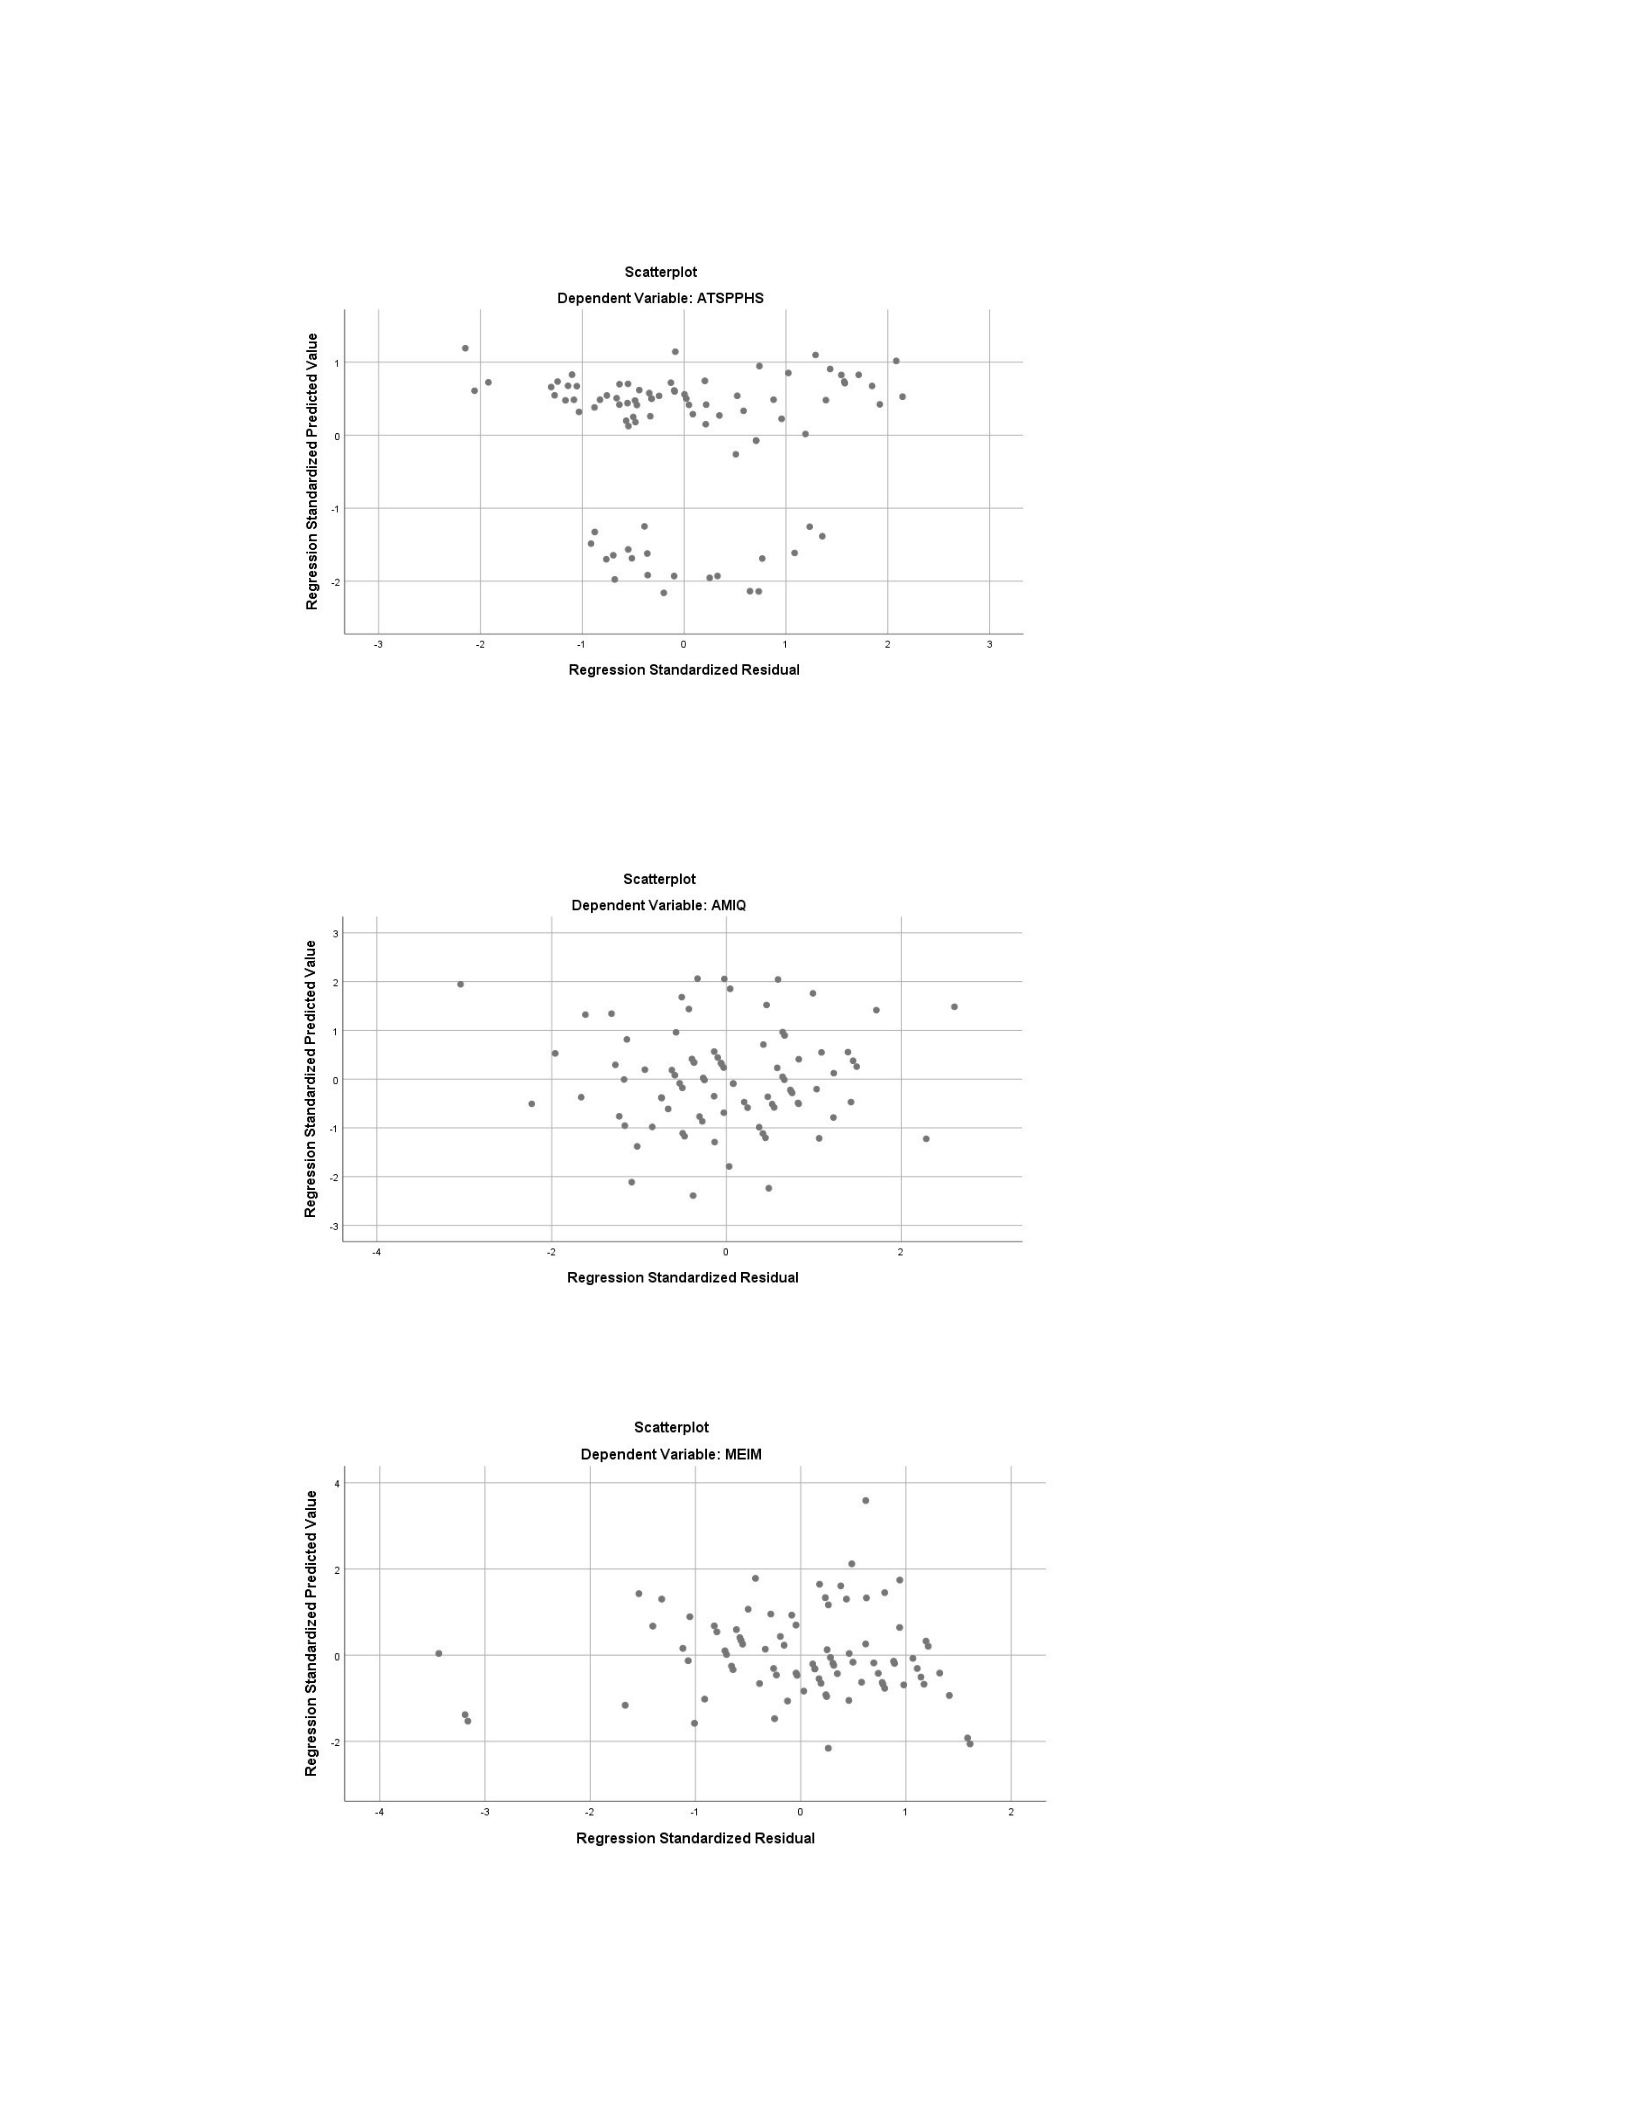
Figure 6. Homoscedasticity of ATSPPHS.
Figure 7. Homoscedasticity of AMIQ.
Figure 8. Homoscedasticity of MEIM-R.
Figure 9. Homoscedasticity of SSOMI.
Reliability Analysis
I analyzed the reliability of data collected by the four surveys using
Cronbach's alpha, which is a measure of the intercorrelations among a set of items
(Babbie, 2010; Marshall, 2016; Garson, & Statistics Associates Publishing, 2012).
Cronbach's alpha is a measure of internal consistency and considered to be a measure
of scale reliability. A value of Cronbach's alpha statistic above .70 is considered to be
a good value whereas above .80 is better and above .90 is taken as the best value
(Garson, & Statistics
Associates Publishing, 2012). As shown, the score values have good reliability values as
shown in table 6 with the exception of AMIQ scale with Cronbach’s Alpha of .62, which
is considered to be marginally accepted with what has been obtained in previous
research.
Table 6
Reliability Statistics
Survey N of items Cronbach's Alpha
Ethnic Identity 6 .89
Attitudes Toward Mental
Illness
5 .62
Self-Stigma of Mental
Illness
10 .74
Attitudes Toward Seeking
Professional
Psychological Help Scale
29 .83
Multiple Regression Analysis Results
A multiple linear regression analysis was used to determine the predictive
relationships between the independent variables of ethnic identity, stigmas against
mental illness, perceptions of mental illness, and the dependent variable of attitudes
towards seeking professional help for mental health issues among African American
college students after controlling for gender.
Table 7 displays results of ANOVA in which the F-ratio is .034 for model 1. It
examines whether the overall model of regression is a good fit for the data or not. The
table displays that the model is not a significant predictor of the predicted variable, F (3,
81) =.034, p >.99 (i.e., the model of regression is a not good fit of the data). In the table
of ANOVA, the F-ratio is 1.91 for model 2. It examines whether the overall model of

regression is a good fit for the data or not. The table displays that the model is not a
significant forecast of the predicted variable, F(4, 80) =1.909, p > .11 (i.e., the model of
regression is not a good fit of the data).
Table 7
ANOVA Results for Overall Regression Model
Model Sum of df Mean F Sig.
Squares Square
1
Regression
Residual
15.19
12040.75
3
81
5.06
148.65
.03
.99b
Total 12055.95 84
2
Regression
Residual
1050.68
11005.26
4
80
262.67
137.56
1.91
.11c
Total 12055.95 84
a. Dependent Variable: ATSPPHS
b. Predictors: (Constant), (SSOMI) Self-Stigma of Mental Illness Ethnic
Identity (MEIM-R), (AMIQ) Attitudes to Mental Illness Questionnaire
c. Predictors: (Constant), (SSOMI) Self-Stigma of Mental Illness, Ethnic Identity-
(MEIM-R), (AMIQ) Attitudes to Mental Illness Questionnaire, What is your gender?
Table 8 presents results from the regression model summary. The results from
the regression model summary was included in my results section because the
regression model summary showed evidence of a statistically significant model. Based
on the results of model 1, the independent variables were not significant predictors of
the dependent variable, Attitudes toward seeking help for mental illness. In model 2,

the gender variable was included in the analysis which indicated that the model was
significant (F(3, 81) = .7.53 R2 = .09, p =< .05.
Table 9 presents a summary of unstandardized and standardized coefficients.
The results revealed that attitudes toward mental illness, ethnic identity and self-
stigma of mental illness were not significant predictors of the dependent variable
attitudes toward seeking help for mental illness. After including the gender variable in
model 2, the results indicated that gender was a significant predictor of the dependent
variable, Attitudes toward seeking help for mental illness., β.-.30, t = -2.74, p < .05.
Since gender had an impact on the dependent variable, Attitudes toward seeking help
for mental illness. I conducted an independent samples t-test to check whether there
was a significant difference in the average score of ATSPPHS based on gender.
Table 8
Regression Model Summary
Mode
l
r r2 Adjusted
r2
SE of
the
Estimat
e
r2 Change Change Statistics F
Change
df d
1 f
2
Sig. F
Change
Durbin-
Watson
1 .04a
.0
0 -.04 12.19 .00 .034
8
3
1
.99
2 .30b
.0
9 .04 11.73 .09 7.53
8
1
0
.01 1.36
a. Predictors: (Constant), SSOMI Self-Stigma of Mental Illness, Ethnic Identity,
Attitudes to Mental Illness Questionnaire
b. Predictors: (Constant), Self-Stigma of Mental Illness, ETHNIC IDENTITY,
Attitudes to Mental Illness Questionnaire, What is you gender?

c. Dependent Variable: - Attitudes Toward Seeking Professional Psychological Help
Scale

Table 9
Regression Model Results
Model Unstandardized
Coefficients
Standard
ized
Coeffici
ents
T Sig
.
Correlations Collinearit y
Stati
stics
B Std. Error Beta ZeroorderPartial Part Toler ance VIF
1 (Constant) 49
.1
2
8.69 5.
65
.00
Ethnic
Identity
.0
7
.26 .03 .2
7
.79 .03 .03 .03 .98 1.02
Attitudes to
Mental Illness
Questionnaire
.0
2
.42 .01 .0
5
.96 .02 .01 .01 .90 1.11
Self-Stigma
of Mental
Illness
-
.0
2
.20 -.01 -
.1
3
.90 -.02 -.01 -.01 .92 1.09
2 (Constant) 60
.7
3
9.37 6.
48
.00
Ethnic
Identity
.1
2
.26 .05 .4
6
.64 .03 .05 .05 .97 1.03
Attitudes to
Mental Illness
Questionnaire
.0
7
.40 .02 .1
8
.85 .02 .02 .02 .90 1.12
Self-Stigma
of Mental
Illness
-
.1
0
.19 -.06 -
.5
1
.61 -.02 -.06 -.05 .90 1.11
Gender 8.
37
3.05 -.30 2.
74
.00 -.28 -.29 -.29 .97 1.03

a. Dependent Variable: (ATSPPHS) Attitudes Toward Seeking Professional
Psychological Help Scale
In this study, I examined the degree to which the independent variables (i.e.,
scores on the Ethnic Identity, Self-Stigma of Mental Illness, Attitudes to Mental
Illness
Questionnaire Scales) predicted the dependent variable (scores on the Attitudes
Toward Seeking Professional Psychological Help Scale). I, therefore, accepted the
null hypothesis, which posited that stigma against mental illness and perceptions of
mental illness were not statistically significant predictors of attitudes toward help
seeking for mental illness of African American college students attending an HBCU.
However, results from an ad hoc analysis revealed statistically gender differences in
the dependent variable, which was attitudes toward seeking professional help for
mental illness
(ATSPPHS scores).
Descriptive Statistics with the Gender Variable
Table 10 presents descriptive statistics for each variable in the study based on
gender. The total Ethnic Identity score for females (M= 23.38, SD=5.38) in comparison
to males (M=24.30, SD= 4.04) indicates that males, in general, had higher overall
scores related to ethnic identity compared to females. The Attitudes to Mental Illness
Questionnaire (AMIQ) scores were further assessed for males and females. AMIQ
scores showed that females (M=-2.34, SD= 2.99) had slightly more negative attitudes
toward mental illness than males (M=-1.55, SD=4.44).
Table 10
Independent T-Test Descriptive Statistics
Gender N Mean
Std.
Deviation
Std. Error
Mean
Ethnic Identity (MEIM-R) Female 65 23.38 5.37 .66
Male 20 24.30 4.04 .90
Ethnic Identity Score 1 Female 65 3.82 .94 .11
Male 20 3.93 .69 .15
Ethnic Identity S 2 Female 65 3.98 .95 .11
Male 20 4.16 .84 .18
(AMIQ) Attitudes to Mental Illness
Questionnaire
Female 65 -2.34 2.99 .37
Male 20 -1.55 4.44 .99
(SSOMI) Self-Stigma of Mental
Illness
Female 65 31.46 7.04 .87
Male 20 28.85 6.69 1.4
(ATSPPHS) Attitudes Toward
Seeking Professional Psychological
Help Scale
Female 65 51.85 12.28 1.52
Male 20 43.90 8.71 1.94
Attitudes Toward Seeking
Professional Psychological Help
Scale (ATSPPHSRECOGNITION)
Female 65 12.15 2.92 .36
Male 20 15.30 3.02 .67
Attitudes Toward Seeking
Professional Psychological Help
Scale (ATSPPHSTOLERANCE)
Female 65 7.49 2.40 .30
Male 20 9.70 2.86 .64
Attitudes Toward Seeking
Professional Psychological Help
Scale
(ATSPPHSINTERPERSONAL)
Female 65 10.76 3.62 .44
Male 20 13.65 3.03 .67
Attitudes Toward Seeking
Professional Psychological Help
Scale (ATSPPHSCONFIDENCE)
Female 65 14.09 3.45 .42
Male 20 15.55 2.99 .67

The average score for self-stigma of mental illness (SSOMI scale) for African
American students participating in this study was (M= 30.85, SD=7.01). However,
females (M= 31.46, SD= 7.04) scored higher than males (M=28.85, SD= 6.70),
indicating higher self-stigma associated with mental illness. When it comes to the
dependent variable ATSPPHS, females (M=51.85, SD= 12.28) scored overall higher
in comparison to males (M=43.90, SD=8.71
Independent Samples t test
Since this study took into consideration that gender might have an impact on
responses for African American college students on the topic of mental health
stigma (Topkoya, 2014; Colvin, Bollock, George, 2016), an independent samples t-
test was completed on each variable used in this study. The t-test is a frequently
used test of statistical significance for comparing means (Babbie, 2010). An
independent samples TTest was conducted to compare the dependent variable scale,
attitudes towards seeking professional psychological help, for African American
males and females as shown in Table 10 and 11. There was a statistically significant
difference in the total ATSPPHS score for females (M = 51.85, SD = 12.28)
compared to males (M = 43.90, SD = 8.71), conditions; t(83) = 2.69, p = .01. These
results indicated African American female college students compared to African
American male college students had more favorable attitudes towards seeking
professional psychological help. Specifically, results suggest that females may be
more receptive to seeking help for mental illness compared to males.

More specifically, in further assessing whether or not there was a significant
difference in using the ATSPPHS scale, each subcategory scale (i.e., Recognition of
need for psychotherapeutic help, stigma tolerance, interpersonal openness,
confidence in mental health practitioner subscale) was further assessed to see if
gender is a significant variable to consider. For the ATSPPHS subscale titled,
recognition of need for psychotherapeutic help, there was a significant difference for
females (M = 15.61, SD = 4.88) and males (M=12.50, SD=2.62), conditions; t(83) =
2.72, p = .01. These results suggest that females are more likely to admit to needing
mental help in comparison to African American male college students attending
HBCUs. When assessing the stigma tolerance subscale, there was not a significant
difference for females (M = 8.58, SD = 2.96) and males (M = 7.50, SD = 1.96),
conditions; t(83) = 1.53, p = .13. Results suggest that African American college
students, whether male or female have similar tolerance level mental health stigma.
For the interpersonal openness subscale, there was a significant difference for
females (M = 11.72, SD=4.00) and males (M = 8.85, SD = 2.81), conditions; t(83) =
2.98 , p = .00. These results suggest that African American female college students
are more open to engage or communicate about seeking professional help in
comparison to African American male college students. There was not a significant
difference for females (M = 15.92, SD = 4.07) and males (M = 15.05, SD = 4.60),
conditions; t(83) = .81 , p = .42 for the confidence in mental health practitioner

subscale. This result indicates that there is not a difference with African American
college students sense of confidence with their mental health provider.
An independent samples t-test was conducted to compare the variable
assessing self- stigma of mental illness (SSOMI) for African American male and
female college students. There was not a significant difference in the total SSOMI
score for females (M
= 31.46, SD = 7.04) and males (M = 28.85, SD = 6.69), conditions; t(83) = 1.47, p = .15.
These results suggest that there is no difference with African American college students
attending HBCUs assessing their attitude towards or willingness to seek mental health
treatment from a professional mental health provider.
When it comes to assessing the variable ethnic identity, an independent
samples ttest was also conducted to compare African American’s relation to their
ethnic identity for male and female college students. There was not a significant
difference in the total
Ethnic Identity scale (M = 23.38, SD = 5.37) for females and males (M = 24.30, SD
= 4.04), conditions; t(83) = -.70, p = .48. For the ETHNIC IDENTITY exploration
subscale, although African American college male students averaged slightly higher,
there was not a significant difference (M = 3.82, SD = .94) for females and males (M
= 3.93, SD = .69), conditions; t(83 ) = -.49 , p =.62. Results indicate that there is no
difference for African American college students attending HBCUs engagement in
learning about their own cultural practices. In addition, although males scored

higher on the commitment subscale score, there was not a significant difference in
the Ethnic
Identity commitment scale (M = 3.97, SD = .95) for females and males (M = 4.16, SD
= .84), conditions; t(83) = -.79, p = .43. Results suggest that there was not a
statistically significant difference between African American male college students’
affirmation of their ethnic group in comparison to African American female college
students.
An independent samples t-test was also conducted to assess the variable scale
AMIQ for African American male and female college students. There was not a
significant difference in the total AMIQ score for females (M = -2.34, SD = 2.99) and
males (M = -1.55, SD = 4.44), conditions; t(83) = -.91, p = .36. These results suggest
that African American college students in this study did not have a difference in
perception towards mental illness.
Table 11
Independent Samples T-Test
Levene's
Test for
Equality
of
Variances
t-test for Equality of Means
F Sig. T Df
Sig.
(2taile
d)
Mea
n
Diff
eren
ce
Std.
Erro
r
Diff
eren
95%
Confidence
Interval of
the
Difference
ce Lower Uppe
r
Ethnic
Identity
Equal
variances .15
assumed
.70 -.70 83.0
0 .48 -.92 1.30 -3.51 1.68
Equal
variances not
assumed
-.82 41.6
6 .42 -.92 1.12 -3.18 1.35
Ethnic
identity
Score 1
Equal
variances .76
assumed
.38 -.49 83.0
0 .62 -.11 .23 -.57 .34
Equal
variances not
assumed
-.58 42.4
0 .57 -.11 .19 -.51 .28
Ethnic
Identity
Score 2
Equal
variances .02
assumed
.90 -.79 83.0
0 .43 -.19 .24 -.66 .29
Equal
variances not
assumed
-.84 35.4
2 .41 -.19 .22 -.64 .26
Attitude
Towards
Mental
Illness
Equal
variances 5.37
assumed
.02 -.91 83.0
0 .36 -.79 .86 -2.51 .93
Equal
variances not
assumed
-.74 24.5
3 .46 -.79 1.06 -2.97 1.40
Self-Stigma
of Mental
Illness
Equal
variances .03
assumed
.86 1.47 83.0
0 .15 2.61 1.78 -.93 6.15
Equal
variances not
assumed
1.51 32.9
9 .14 2.61 1.73 -.92 6.14

Attitudes
Toward
Seeking
Professional
Psychologica
l Help Scale
Equal
variances 2.13
assumed
.15 2.6 83.0
0 .01 7.95 2.56 2.07 13.8
3
Equal
variances not
assumed
3.21 44.4
0 .00 7.95 2.47 2.96 12.9
3
Attitudes Equal
Toward variances .03
Seeking assumed
.87 -4.17 83.0
0 .000 -
3.15 .75 -4.65 -1.64
Professional
Psychologica
Equal l Help
Scale variances not
(ATSPPHSR
assumed
ECOGNITI
ON)
-4.09 30.7
4 .00 -
3.15 .77 -4.71 -1.58
Attitudes Equal
Toward variances .97
Seeking assumed
.33 -3.43 83.0
0 .00 -
2.21 .64 -3.49 -.93
Professional
Psychologica
Equal l Help
Scale variances not
(ATSPPHST assumed
OLERANCE
)
-3.12 27.7
3 .00 -
2.21 .71 -3.66 -.76
Attitudes Equal
Toward variances .52
Seeking assumed
.47 -3.22 83.0
0 .00 -
2.88 .89 -4.66 -1.10
Professional
Psychologica
Equal l Help
Scale variances not
(ATSPPHSI assumed
NTERPERS
ONAL)
-3.54 37.2
3 .00 -
2.88 .81 -4.53 -1.23

Equal
Attitudes
variances .54
Toward assumed
.47 -1.70 83.0
0 .09 -
1.46 .86 -3.16 .25
Seeking
Professional
Psychologica
Equal l Help
Scale variances not
(ATSPPHSC assumed
ONFIDENC
E)
-1.83 35.8
9 .07 -
1.46 .80 -3.07 .16
Summary
In Chapter 4, an overview of the data collection process was discussed. Data
was analyzed from survey responses of 85 college students which were used to answer
survey questions on SurveyMonkey.com. Any discrepancies within the recruitment
process and statistical assumptions were reviewed in this chapter. The data was used
to examine the relationships between one’s ethnic identity, perception of mental
illness, and attitude toward seeking professional help for mental illness among African
American college students attending HBCUs. Several methodologies were analyzed to
test for variable significance. Results from the multiple regression analysis showed
that the independent variables self-stigma of mental illness (SSOMI), attitudes towards
mental illness questionnaire (AMIQ), and multi-group ethnic identity (MEIM-R)
measure were not a significant predictor of attitudes toward seeking professional
psychological help (ATSPPHS). Therefore, the null hypothesis was accepted, and the
alternate hypothesis was rejected. An independent t-test was further used to assess

impact of gender on each variable assessed in this study. Results indicated that a
greater number of African American female college students compared to African
American college males had favorable attitudes towards seeking professional
psychological help. There was not a significant difference in scores assessed on the
SSOMI, AMIQ, and the MEIM-R scale for females or males. The interpretation of the
findings, recommendations for future research, and implications for positive social
change are discussed in Chapter 5.

Chapter 5: Discussion, Conclusions, and Recommendations
Introduction
In this study, I assessed the predictive relationships between African
American college students’ ethnic identity, perceptions of mental illness, stigma
against mental illness, and their attitudes towards seeking help for mental illness.
Findings from a linear multiple regression analysis revealed that ethnic identity,
stigma, and perceptions of mental illness were not statistically significant predictors
of African American college students’ attitudes toward seeking professional help for
mental illness. However, a post hoc analysis revealed that gender was a significant
predictor of attitudes toward helpseeking behavior for mental illness among African
American college students.
In this chapter, I further summarize the finding of this research study, which
includes an interpretation of the findings in the context of the theoretical framework
and the existing literature. Also discussed in this chapter are the limitations of the
study. In addition, recommendations for further research and implications for social
change are included.
Interpretation of the Findings
The study was guided by one research question: What are the predictive
relationships between ethnic identity, stigmas against mental illness, perceptions of
mental illness, and attitudes towards seeking professional help for mental health
issues among African American college students after controlling for gender? In the

following section, I present an interpretation of the findings relative to each variable
used in this study.
The focus of this study was to examine the relationship between ethnic
identity, the stigma of mental illness, perceptions, and help-seeking among African
American college students (Villatoro & Aneshensel, 2014; Vinson et al., 2014).
There was a limited amount of literature that focused on help seeking for professional
help among African American college students attending HBCUs. Results from this
study revealed that ethnic identity was not a significant predictor of African
American college students’ attitudes towards seeking professional psychological
help. Therefore, the null hypothesis was accepted. However, gender was a significant
predictor of seeking professional psychological help. Results showed that African
American college females may be more receptive to seeking help for mental illness
compared to African American college males. Overall findings of this study were
unexpected as I expected the stigma of mental illness, perceptions of mental illness,
and ethnic identity to be predictors of attitudes towards seeking professional help.
Modified Labeling Theory
The conceptual framework used for this study was based on the modified
labeling theory. According to the modified labeling theory, labels can have a
negative impact on individuals diagnosed with a mental illness (Link et al., 1989).
Labels can also lead to negative outcomes (Link et al., 1989). Negative outcomes of
being labeled with mental illness can include feeling discriminated against, social

withdrawal, fear of being rejected, feeling devalued, and a lack of treatment seeking
(Link et al., 1989; Link &
Phelan, 2013).
The premise of the modified labeling theory can be used to explain how
beliefs impact a person’s views of mental health illness, their perceptions of mental
illness, and their attitudes toward seeking help for mental illness. Findings from this
study supported the premises of modified labeling theory as it relates to attitudes
toward seeking professional psychological help for mental illness after controlling
for gender. Findings from my study indicated that gender was a predictor of seeking
professional help. Findings from my study revealed that African American males
had less favorable attitudes towards seeking professional help. African American
college student males were also less open to communicate the need to seek
treatment. Results for the Attitudes Towards Mental Health Scale indicated that
females had slightly more negative attitudes than males when it came to assessing
perceptions of a stigmatized individual. Findings as they related to the self-stigma
scale and attitudes towards mental health were not completely situated within the
theoretical foundation, which means that results were not aligned with the premise
of the labeling theory. Part of the reason for this result is that the labeling theory
partly depicts from the perspective that the stigmatized individual’s behaviors are a
direct result of being labeled. Results in this study did not show that perceptions of
stigma were a significant predictor of help seeking. Overall, results from my study
were aligned with the modified labeling theory as it related to attitudes toward

seeking professional psychological help for mental illness but not as it related to the
stigma of mental illness and the perceptions of mental illness.
Stigma of Mental Illness and Attitudes Toward Seeking Help for Mental Illness
Several researchers have proposed that the stigma of mental illness continues
to be a barrier to mental health treatment (Haynes et al., 2017; Lannin et al., 2016;
Masuda et al., 2012). However, there are research studies that addressed the
relationship between stigmas against mental illness and attitudes toward seeking
treatment for mental illness that did not support those assertions. Findings from my
study were consistent with results found by Lally et al. (2013), which showed that
perceived public stigma was not a predictor of help seeking intentions for university
students. However, results from my study contradicted findings from other research
that showed that the stigmas against mental health were related to help seeking for
mental illness. For instance, Clement et al. (2014) reported that participants with
strong mental health stigmas were less likely to seek help for mental health illness.
However, Clement et al. included youth and adults living in the United States,
Canada, Europe, Australia, and New Zealand. Clement et al. indicated that
generalizability to the population of African American college students in the United
States is low. Fripp and Carlson (2017) examined the relationship between mental
health stigma and help seeking for individuals diagnosed with mental illness. Fripp
and Carlson revealed that African American and Latino participants’ stigma of
mental health illness was a factor that hindered their seeking professional help for
mental illness. However, findings from my study contradict results from the study

completed by Fripp and Carlson as results in my study did not indicate that the
stigma of mental health illness was a predictor to seeking professional help. In
another study, Vogel (2017) assessed the relationships between public stigma, self-
stigma, and attitudes toward seeking mental health treatment, and the results showed
that stigma against mental health stigma was a significant predictor of help seeking
for mental illness.
In an earlier study, Evans-Lacko et al. (2012) assessed the relationships
between stigma and help seeking for mental illness among participants from about
14 different European countries. Results showed that higher rates of help seeking
were found in countries where there were fewer stigmatizing attitudes about mental
illness. EvansLacko et al. also reported lower rates of self-stigma for those living in
countries where individuals felt more comfortable openly communicating with
others with mental illness. Findings from my study contradicted findings from
Evans-Lacko et al. in that results from my research revealed that higher rates for
seeking help for mental illness when individuals reported less stigma towards mental
illness. Results from my study did not show any statistically significant predictive
relationship between seeking help for mental illness and stigma towards mental
illness.
Findings from my research also contradicted findings from Lannin et al.
(2016), which showed that university students in need of mental health treatment
were reluctant to access mental health treatment information if they experienced
high levels of selfstigma. However, students from my study were African American

college students from the United States in comparison to the study completed by
Lannin et al. The majority of participants in Lannin et al.’s study were European
American students, thus limiting the generalizability of the results to other
racial/ethnic groups.
Findings from my research also contradicted findings from Mendoza et al. (2015)
where they assessed whether mental health stigma impacted attitudes toward help
seeking for undergraduates in Georgia. Results from the study indicated that mental
health stigma was a unique predictor of help-seeking attitudes (Mendoza et al., 2015).
Findings were not limited to an inclusive population of African American college
students attending HBCUs, which limits generalizability of the results to the racial/ethnic
group used for my study.
Furthermore, Hall and Sandberg (2012) discovered that stigma was a barrier to
treatment among African Americans. Participants used in Hall and Sandberg’s study
were not limited to college students. Therefore, the generalizability of findings from
Hall and Sandberg to African American college students is limited. Findings from my
research contradicted findings found in Hall and Sandberg’s study as stigma was not a
significant predictor to seeking treatment for mental illness.
Attitudes Towards Mental Illness and Help Seeking for Mental Illness
Findings from my research did not show that perceptions of mental health illness
were a significant predictor of attitude toward seeking treatment for mental health for
African American college students’ attending HBCUs. These results were similar to
results presented by Mesidor and Sly (2014), which revealed that attitudes toward

mental health services were not a significant predictor of intentions of seeking
treatment for mental health. However, findings from my research study contradicted
findings from a study by Pedersen and Paves (2014), which revealed that attitudes
towards seeking treatment were positively associated with perceived public stigma
and personal stigma of mental health among college students. However, Pedersen and
Paves’s study only included White and Asian American students, which limits the
generalizability of the results to African American college students. In another study,
Lally et al. (2013) also found that personal stigma (personal attitude towards mental
illness) was significantly associated with a decreased likelihood of future help-
seeking behavior for mental illness. Results from my study contradict results by Lally
et al. as results from my study did not indicate that attitudes toward mental illness
was a significant predictor of help seeking.
Results from a study completed by Haynes et al. (2017) are also important to
note. The results from my research contradict findings as results from Haynes et al.
(2017) indicated that the perception of mental illness is a barrier to mental health
treatment. Haynes et al.’s (2017) results are indicative of African Americans’
perspective of how they view individuals diagnosed with a mental health diagnosis.
Furthermore, the results from the Haynes et al. (2017) study are also an example of
how an individual’s perception may be associated with whether or not African
Americans seek professional treatment. Findings from my study differed from the
Haynes et al. (2017) study as my study indicated that the perception of mental illness
was not a barrier to seeking professional help.

Ward et al. (2013) also discovered that negative perceptions of seeking help
for mental health issues were negatively associated with their desire to seek mental
health treatment in a sample of middle-aged African Americans. Findings from my
study are also contradictory to findings found in the Ward et al. (2013) study
because negative perceptions of attitudes towards mental health were a predictor of
seeking mental health treatment. In addition, Gaston, and Doherty (2017) also
reported that negative perceptions of mental health care among American and/or
foreign-born Blacks was a barrier to seeking mental health treatment. However,
generalizability of results from the Gaston and Doherty (2017) may not extend to
African American college students attending HBCUs. Findings from my research
study did not support findings from the study completed by Gaston and Doherty
(2017) as the results from my study indicated that perceptions of mental illness was
not a significant predictor of seeking mental health treatment.
Ethnic Identity and Attitudes Toward Seeking Professional Psychological Help
Findings from my research differed from findings of previous research that
have been completed on the topic of ethnic identity as it relates to one’s mental
health and help-seeking behavior. For instance, Britian et al. (2013) found that
African American college students who had positive ethnic affirmations had more
favorable attitudes toward mental health illness. Results from my study did not align
with results from Britian et al. (2013) as findings in my research did not show a
significant relationship between ethnic identity and perceptions towards mental
illness. Cheng et al. (2013) also found that African Americans who possessed high

levels of ethnic identity had decreased self-stigma toward seeking help for
psychological issues. Findings from my research study were different from findings
of Cheng et al. (2013) as there was not an association found with ethnic identity and
treatment seeking behavior mental illness.
In a study completed by Hooper et al. (2012), the researchers implied that an
individuals’ ability to identify with the ethnic culture of their mental health provider
was a significant predictor in African American college students’ seeking mental
health treatment. Findings from my research study are contradictory to findings
found in the Hooper et al. (2012) study as results indicated that one’s ethnic identity
is a predictor in seeking mental health treatment.
Gender, Self-Stigma, Attitudes Towards Mental Illness, Ethnic Identity, and Help
Seeking
A post hoc comparison was completed to further assess whether gender was
a statistically significant predictor for stigma of mental illness, attitudes towards
mental illness, ethnic identity, and attitudes towards seeking mental health treatment
in my study. Findings in my study showed that females scored higher than males on
the SelfStigma of Mental Illness (SSOMI) scale, which indicated higher self-stigma
associated with mental illness for females compared to males. This result is
interesting to note, as later reported in the chapter, although this scale showed higher
self-stigma among females, according to the ATSPPPHS scale, females were more
receptive to seeking professional mental health help.

Results from my study do align with findings from previous research regarding
differences between how males and females view mental illness and seek treatment for
mental illness. For example, Topkaya (2014) found that gender and self-stigma
significantly predicted psychological help-seeking for mental illness. Findings from
my research confirm that gender is a significant predictor of attitudes toward seeking
psychological help and contradict that self-stigma is a significant predictor of attitudes
toward seeking psychological help. Topkaya (2014) found that males were more likely
to experience self-stigma and public stigma compared to females. Findings from my
study contradict findings from the Topkaya study as the results showed that males in
my study reported lower levels of self-stigma than females in the study.
In addition, perceptions of mental illness did not differ across gender for the
sample used in my study. In my study, females scored slightly higher in comparison
to males on the Attitudes toward Mental Illness (AMIQ) questionnaire showing
overall negative attitudes towards mental illness. In the study completed by Watson
and Hunter (2015), results showed that African American women endorsed stigma
concerns and exhibited apprehensions such as anxiety as it relates to mental health.
Results from Watson and Hunter (2015) indicated that African American women had
concerns about being judged negatively. Findings from my research study support
the findings from the Watson and Hunter (2015) study as females in my study had
more negative perceptions towards mental health in comparison to males.
As previously mentioned for this study, gender was a significant predictor of
help-seeking behavior for African American college students attending HBCUs. A

post hoc comparison was completed in regards to gender and the dependent variable
Attitudes Toward Seeking Professional Psychological Help (ATSPPHS). Results
from my research showed that African American female college students had more
favorable attitudes towards seeking professional treatment for mental health in
comparison to African American college male students attending HBCUs. These
results were consistent with findings from Colvin et al. (2016) which showed that
females tended to display more positive attitudes toward help-seeking behaviors in
comparison to males. Masuda et al.’s
(2012) results revealed that African Americans’ mental health stigma was uniquely
associated with help-seeking attitudes after controlling for gender and previous
experience of seeking professional psychological services. Findings from my research
are consistent with results from Masuda et al. (2012) which indicated that gender was a
predictor of seeking mental health treatment. Masuda et al. (2012) reported a negative
association between mental health stigma and help-seeking attitudes. Findings from
Masuda et al.’s (2012) study are relevant to report as it demonstrates the significance of
considering gender as a predictor variable to attitudes toward mental health treatment
seeking. Similar to my study, the majority of participants in the Masuda et al., (2012)
study were primarily female which limited generalizability of the results from the study
to other studies with samples that contain more males.
Williams and Cabrer-Nguyen (2016) reported that African American women
were more likely than men to utilize mental health services. Findings from my
research study were consistent with results from Williams and Cabrer-Nguyen (2016)

study as results from my study showed that females were more likely to seek mental
health treatment in comparison to males. In addition, results from Ward et al. (2013),
indicated that African American men were noted to be less open to seeking
professional help in comparison to women. Findings from my study confirm results
found in the study completed by Ward et al. (2013) which indicated that females have
more favorable attitudes toward seeking professional help.
Limitations
This study did have limitations. First, there is a possibility the sample used in this
study is not representative of African American college students attending HBCUs across
the United States. The outcome of the results may have been different if the study were
replicated using a larger sample of African American college students attending HBCUs
in the United States. This study was limited to African American college students
attending three HBCUs in Atlanta, GA. Private HBCUs in Georgia are representative of
a small percentage of private HBCUs across the United States.
In addition, the small sample size could further limit the generalizability of
the results. Smaller samples could lead to sampling bias or result in a high
variability in the findings that do not represent the general population (Garson,
2016). Sampling bias and high variability in the findings can be a disadvantage in
using this method for recruitment. For instance, although males and females
volunteered to participate in this study, there were fewer males that participated in
this study. The lower number of males in this study may have been due to delays in

the recruitment process, early on, to potential male participants from Morehouse
college.
In addition, limiting the selection of institutions to only private HBCUs
further limits the generalizability of the findings. All schools used in this study were
private institutions. If the study were conducted with a sample of African American
students from both public and private institutions, the results may have been
different. Also, the results may have been different if the sample had included
students from varying socioeconomic backgrounds. Previous research has indicated
that higher socioeconomic backgrounds has been associated with seeking treatment
for mental illness (McLaughlin et al., 2012; Evans, 2016). Previous research has
indicated that individuals with lower socioeconomic status living in rural areas tend
to lack access to mental health professionals (Evans, 2016).
This study did not include other demographic factors such as socioeconomic
factors (i.e., family’s income class, parent’s education level, parental marital status,
family’s occupational status) (Holden et al., 2012; Khumalo, Temane & Wissing,
2012; Pico et al., 2016) or academic classification (i.e., freshman, sophomore, junior,
senior) as previous research studies have showed that demographic factors could be a
predictor to help seeking for treatment. In addition, the trust of mental health
providers (Whaley, 2011) or program of study (Theriot & Lodato, 2012; Zellman,
2014) were not included which may also be significant predictors to help seeking of
African American college students. For example, mental health problems have been
significantly associated with sex, race/ethnicity, religiosity, relationship status, living

on campus, and financial situation as found in a study completed by Eisenberg, Hunt,
and Speer (2013). Therefore, it is of interest to further examine how these factors
impact help seeking.
Another limitation which may have impacted the generalizability of the results
is that only the vignette which depicted a stigmatized individual was utilized to
measure participants’ attitudes toward mental illness. The AMIQ was originally
developed to consist of five short vignettes that describe an imaginary individual with
mental illness.
These vignettes were then followed by five questions to assess individual’s perception
of the subject and their willingness to interact with the individual. The use of only one
vignette may have attributed to the marginally accepted reliability in comparison to
what has previously been reported in other studies. As reported by the original authors
of the AMIQ scale, content validity and reliability were reported as high, as indicated
by
Cronbach’s alpha score, factor analysis, and test-retest correlation coefficients (Luty
et al., 2006). Using only one vignette may have limited the generalizability of the
results of my study in comparison to other studies that utilized all five vignettes.
Recommendations
It is suggested that further research is conducted with an overall comparison of
males to females as it relates to understanding the relationship between one’s ethnic
identity, attitude, and perception of seeking professional psychological help. Results

from the data analysis revealed that ethnic identity, perceptions of mental illness, and
mental health stigma were not statistically significant predictors of attitudes toward
seeking professional help for mental illness among African Americans attending
HBCUs. However, results did indicate that gender was a significant predictor for
attitudes toward help seeking. I recommend additional studies, using the same
population (i.e., African American college students) and research modality (i.e.,
Quantitative research design), be conducted to confirm these results from my study as
research on this topic is limited.
In addition, the majority of participants for this study were female (76.5%).
Researchers who conduct future studies in this area should consider ways to increase
male participation. A larger proportion of males in the data may have generated
different results. In addition, a redo of this same study (correlational, non-
experimental), using samples from HBCUs across the United States may provide
better generalizability of results. The inclusion of other HBCUs in the United States
would yield larger participation of students and thereby potentially increase the
generalizability of results.
I further suggest that future research focus on African American students
attending HBCUS, specifically to assess whether college campuses are promoting or
presenting mental health awareness campaigns and outreach on HBCU campuses.
This recommendation is being made as results indicated that stigma of mental
illness, perceptions of mental illness, and ethnic identity were not significant
predictors of seeking professional help for HBCU students in my study. I

recommend that future researchers consider conducting a mixed method approach to
assess gender differences in personal experiences with mental illness on campuses
for African American college students attending HBCUs and how this may be a
predictor to help seeking. Gender specific awareness on campuses may help to see if
there are different approaches that need to be taken for males in comparison to
female students when it comes to addressing mental health stigma, perceptions
towards mental health, and attitudes towards mental health help seeking of African
American college students
The use of a mixed method approach that addressed attitudes toward seeking
professional help might produce data that sheds more interest into researching if
campusbased resources used at HBCUs contribute to African American college
students’ insight about seeking treatment for mental illness. A mixed method
approach might also shed light on whether or not participants have had personal
encounters or personal experiences interacting with others diagnosed with mental
illness. It would be interesting to see if those who have had personal encounters
interacting with others diagnosed with a mental illness impacts responses to
questionnaires in comparison to those who have not had any experiences with those
diagnosed with a mental illness. The quantitative portion of the study would
essentially remain the same in addressing predicting the relationship between ethnic
identity, perceptions of mental illness, stigma of mental health, and attitudes toward
seeking professional help for mental illness. Adding a qualitative component would
allow the researcher to address underlying reasons as to perspectives that African

American college students have formed about seeking mental health treatment. Open
ended interview questions would focus on African American college students’
personal interactions with mental illness, other individuals diagnosed with a mental
illness, and their personal experience in utilizing or being knowledgeable of campus
mental health resources. Through the use of open-ended questions students’ exposure
to mental health awareness campaigns or seminars could further be assessed. In
addition, open ended interviews will further allow the researcher to gain greater
insight into how factors listed above impacted African American student’s own
perception of mental illness. It would have been informative to dialogue with
participants from my study regarding specific behaviors and/or experiences that may
have led to their perceptions toward mental illness, their attitudes toward seeking
professional help for mental illness, and beliefs towards the stigma of mental illness.
Implications for Social Change
This study may have implications for positive social change and may
contribute to the literature that addresses the topic of mental health stigma,
perceptions, and help seeking among African American college students attending
HBCUs. Findings from this study has implications for individuals developing
campus-based campaigns and engaging in advocacy efforts to raise mental health
awareness among African American college students. Implications include the
importance of focusing on gender-based campaigns that are catered to meeting the
needs of the population at each university. Mental health advocacy opportunities can
be developed through the use of courses, pamphlets, literature, and workshops

provided on campus. Advocacy efforts can be implemented to encourage positive
engagement or dialogue on the topic of mental health stigma and help seeking for
treatment. A collective effort with input and participation by faculty, staff, and
students of HBCUs. Programs developed can also cater specifically to genders, if
needed, to accommodate differences in attitudes towards seeking professional help
since results indicated that gender was a predictor of attitudes toward seeking
professional help for this study. Since results indicated that ethnic identity, mental
health stigma, and attitudes toward mental illness were not significant predictors of
attitudes towards seeking professional help. Identifying ways to continue to maintain
a reduction in mental health stigma on HBCU campuses through the use of
collaborating with mental health organizations such as Mental Health America of
Georgia and the National Alliance on
Mental Health Illness are recommended (Mental Health of America of Georgia, 2017;
National Alliance on Mental Health, n.d.) .
Conclusion
This quantitative, correlational study examined the predictive relationship
between African American college students’ ethnic identity, perceptions of mental
illness, stigma against mental illness, and their attitudes towards seeking help for
mental illness. Findings from my study indicated that ethnic identity, stigma against
mental illness, and perception towards mental illness were not significant predictors
of attitudes toward seeking professional help. As previously mentioned in this
chapter, results from my study were contrary to research previously conducted

indicating that mental health stigma (Clement et al., 2014; Vogel, 2017), the
perception towards metal health stigma (Pedersen & Paves, 2014; Schibalski et al.,
2017), and ethnic identity (Cheng et al., 2013) were predictors of attitudes of
African American college students attending HBCUs towards seeking professional
help. However, gender was a significant predictor of seeking help for mental health
treatment. Results showed that African American college females were more
receptive to seeking help for mental illness compared to African
American college males attending HBCUs. Overall, the null hypothesis was
accepted. The outcomes from this study indicate that none of the three variables used
had a meaningful relationship towards one’s attitude toward seeking treatment.

