



Infection
(Giddens Ch.45)
Pathogen - a microorganism that has the potential to cause disease. Pathogens come in the forms
of bacteria, viruses, parasites, or fungi.
Infection - the invasion and multiplication of microorganisms in body tissues, which may be
clinically inapparent or result in local cellular injury due to competitive metabolism, toxins,
intracellular replication, or antigen-antibody response. Infections may be (resolving in aacute
few weeks), or (typically lasts longer than 12 weeks, and in some cases is incurable). Anchronic
infection may be (limited to a specific body area) or (spread out to otherlocalized disseminated
areas of the body) or even (affecting the body as a whole or has spread throughout thesystemic
body).
Sepsis - a common type of systemic infection which is the presence of pathogens in the blood or
other tissues throughout the body
Epidemic - where there are more cases of an infectious disease than is normal for the population
or geographic area
Pandemic - a world-wide epidemic of a disease
●Endemic (affects one community)
●Epidemic (affects multiple communities)
●Pandemic (affects whole world *black plague*)
Think! A person in this modern world can travel anywhere in 24 hours! What if someone had an
asymptomatic disease that was infectious?
Classification of the causative microorganism is the most common way to categorize and discuss
infections. Each microorganism elicits a different immune response (dendritic cells help with
modulating this).
Bacterial Infections - bacteria cause cellular injury by releasing toxins. are enzymesExotoxins
released by gram positive bacteria. are part of the bacterial cell wall of gramEndotoxins
negative bacteria that can cause damage even if the bacteria are dead! Diseases caused by
bacterial invasion depends on the type of bacterial pathogen and the area of the body that is
primarily invaded.
Bacteria
●are one-celled organisms
●have no nucleus or cellular organelles
●synthesize DNA, RNA, and proteins
●can reproduce independently
●need a host (suitable environment) to replicate
Viral Infections - viruses cause cellular injury by blocking its genetically prescribed protein
synthesis processes and using the cell’s metabolic processes for the reproduction of the virus.

Disease develops as a result of interference of the normal cellular functioning of the host with
destruction of the virus by the immune system, also requiring death of the host cell (“sad day”).
Viruses
●have a nucleic acid within a protein shell
●require invasion of a host for replication
●may cause disease immediately or remain relatively dormant for years when invading a
host
Fungal Infections - in healthy individuals, fungi don’t cause disease and are contained by the
body’s natural flora. Fungi that cause disease are called . In those that arefungi imperfecti
immunocompromised, fungal infections can lead to death. Some fungal infections such as Tinea
pedis (athlete’s foot) and may develop in an individual with a competent immuneringworm
system.
Fungi
●are microorganisms belonging to the kingdom fungi, which includes yeasts, molds, and
mushrooms
●may grow as single cells (yeasts)
●may grow as multicellular filamentous colonies (molds or mushrooms)
Protozoa/Parasitic Infections - generally infect individuals with compromised immune responses
but disease develop in an otherwise healthy individual when the spores invade organs andmay
stimulate an immune response, interfering with normal functioning of the organ system.
Protozoa
●have a subcategory termed “parasitic protozoa”
●are found in dead material in the water and soil
●are spread by the fecal-oral route by ingesting contaminated food/water (they have
parasitic spores or cysts - yuck!)
Sometimes an infection will develop that begins as one type and after an additional pathogen is
introduced, a occurs. Fungal infections may develop when treatment for asecondary infection
bacterial infection decimates the body’s natural flora, or bacterial infections may arise when a
debilitated individual is treated for a viral infection. Some bacteria cause disease only when the
host’s immune system is severely compromised (such as seen in HIV infection leading to AIDS).
They are called opportunistic pathogens (similarly, ).opportunistic infections
Some bacteria that are part of the normal flora but can become pathogenic are Mycobacterium
tuberculosis,Staphylococcus epidermidis (if it reaches deep tissues, perhaps by surgery), some
types of , andEscherichia coli Acinetobacter.
Some diseases are communicable before symptoms are evident in the carrier (herpes simplex
virus, varicella-zoster virus, HPV, influenza, or poliomyelitis), whereas others remain
communicable after initial symptoms have subsided (IV and Epstein-Barr virus). Some
infections remain dormant within the host and may resurface as the same or as a different disease
(ex. varicella-zoster virus (VZV) first presents as chickenpox and later may manifest as
shingles).
The “iceberg” concept of infection = 3 levels of infection
1. Largest/underwater section: the vast majority of a population may, at any given time,
carry an infection wherein they are asymptomatic or undiagnosed
2. Smaller section: part of the population presents with an infection that manifests as less
severe, symptomatic disease
3. Smallest “tip of the iceberg” section: people that present with classical, clinical symptoms
or the disease
Epidemiology is important in the study of infection because it is concerned with the inmanner
which a disease spreads through groups of people and the application of this information to the
control of health problems.
Pathogen Invasion - when a pathogen invades the body, a number of immune system responses
are initiated to minimize tissue and organ damage.
●B lymphocytes are activated to differentiate into (for the production ofplasma cells
antibodies), or (in preparation for a future re-exposure).memory cells
●T lymphocytes directly kill the invading organism, secreting lymphokines that attract and
stimulate the activity of macrophages.
●Macrophages and Monocytes initiate phagocytosis.
●The Complement System (MAC) is activated to enhance the entire immune response.
Some tissue damage will occur as a result of endotoxins released by the pathogen that kill host
cells, neurotoxins that affect nerve impulse transmission, or enterotoxins that damage cells of the
gastrointestinal (GI) tract. The physiological effect of endotoxins may be mild (fever, chills,
weakness, or malaise), or severe (shock syndrome or disseminated intravascular coagulation).
Symptoms associated with the release of exotoxins from various pathogens include profuse
diarrhea (cholera), spastic paralysis (tetanus), phagocyte death (gangrene), and prevention of
nerve impulse transmission (botulesm). Severe exotoxin release may cause septic shock
syndrome, which if not controlled rapidly can lead to death.
Symptoms of (which may develop when severe infections are leftmultisystem organ failure
untreated) may include hypotension, tachycardia, anuria, hypoxia, hypercapnia, seizures, or
coma.
Populations at Risk: consider age, ethnicity, gender, socioeconomic status, geographic area, prior
health history
●of the 10 leading causes of infant death in the United States, bacterial sepsis ranks ninth
and disorders related to short gestation and low birth weight rank third
Individual Risk Factors: consider compromised host because of immunodeficiency and/or
chronic illness, and environmental conditions

Health History: includes questions to assess an individual’s risk for infection, recognize
symptoms associated with infection, and appreciate factors associated with a presenting
infection.
Laboratory Tests
●Complete blood count (WBCs)
○elevated levels of B and T lymphocytes, , and monocytes areneutrophils
indicative of infection, particultary a bacterial or viral infection
○parasitic infections may result in an increase in the number of andbasophils
eosinophils
●Culture and sensitivity
●Radiographic Tests
●Other laboratory tests
Primary Prevention - Hand hygiene & standard precautions, immunizations
Secondary Prevention (Screening) - less effective in controlling infection, but helps identify an
infection with the intent for earlier treatment and reducing transmission
(ex. STDs)
Collaborative Interventions - goal is to eradicate the infection, prevent secondary infection, and
limit damage to the body. (antibiotic agents, antiviral agents, antifungal agents),Antimicrobials
Nutrition and Fluids, are part of these.
Key Terms
Immunity - the immune system is the first line of defense against infection and the body’s
primary method of response to an invading organism
Inflammation - part of the body’s response to a foreign antigen, with many of teh symptoms of
infection being those of the body’s inflammatory response (redness, swelling, pain).
Tissue Integrity - is critical to avoiding infection, with the skin being the largest component of
the immune system. intact tissues are less vulnerable to pathogen entry and form natural barriers
to infection
Stress - whether physical, emotional, or environmental, challenges the immune system and
makes it more vulnerable to damage, less able to respond effectively and efficiently to pathogen
invasion, and more difficult for the body to respond to treatment for an infection
Nutrition and Rest - are necessary for the body to respond to active infection treatment regimens
and support the work of an immune response
CLINICAL EXAMPLES
Pneumonia - infection of the lungs (leading cause of death in children younger than age 5)
●Symptoms include chest tightness, shortness of breath, difficulty breathing, cough, and
fever
●Treated with antibiotics and antiviral drugs
Conjunctivitis, or “pink eye” - is characterized by redness and swelling of the conjunctiva, thick
discharge from the eye with crusting on the eyelids or lashes, and itchy, inflamed eyes. Pain is
not typically associated with the infection, but is easily spread from one person to another.
Conjunctivitis is common in children and adults, but in newborns, if it occurs within 3 weeks of
life, it is often caused by gonococcal or chlamydial infections of the mother (may lead to
blindness if left untreated).
Otitis Media - may be classified into one of three types: acute otitis media (AOM), otitis media
with effusion otitis externa(OME), and (Swimmer’s ear).
●AOM is usually painful and often requires treatment with antibiotics. Other symptoms
include redness of the tympanic membrane, pus, and fever.
●OME is a buildup of fluid in the middle ear without symptoms of infection and is often
caused by viral upper respiratory infections and allergies, generally resolving on its own.
●Swimmer’s ear is an infection of the ear and outer ear canal. Treatment with antibiotics is
usually required.
Hepatitis (A,B,C) - inflammation of the liver, leading cause of liver cancer, and the most
common cause of liver transplantation. Significant underreporting of HBV and HCV is
acknowledged due to asymptomatic infections.
●Acute onset of symptoms are discrete (nausea, vomiting, fever, malaise, dark urine,
jaundice). Ascites develops later in disease progression.
Human Papillomavirus (HPV) - the most common sexually transmitted infection, with more than
40 types. It is typically passed through genital contact during vaginal, anal, or oral sex. HPV tests
can be used to screen for cervical cancer. A vaccination is available to men and women against
the types of HPV that most often lead to cancer (given at the age of 11 or 12 years).
●Symptoms of HPV may develop years after exposure and may lead to genital warts and
cancer.
●HPV is so common that the CDC estimates that most sexually active men and women
will get at least one type of HPV sometime in their life.
*Healthcare acquired MRSA is the most severe form of MRSA. People at risk include patients
and visitors of patients in healthcare settings.
Potter Ch. 29
Patients in all healthcare settings are at risk for acquiring infections because of:
●lower resistance to pathogens
●increased exposure to pathogens (some may be antibiotic resistant)
●invasive procedures (ex. surgery)
Healthcare workers are at risk for exposure to pathogens as a result of contact with:
●patient blood
●bodily fluids
●contaminated equipment and surfaces

By practicing basic infection prevention and control techniques, you avoid spreading
pathogens to patients and sustaining an exposure when providing direct care. Healthcare workers
protect themselves from contact with infectious material, and sharps injury, and exposure to a
communicable disease by applying knowledge of the infectious process and using appropriate
personal protective equipment (PPE). Increases in (MDROs),multidrug-resistant organisms
healthcare-acquired infections hepatitis B virus(HAIs), and concern about diseases such as
(HBV) and (HIV) infection, andhepatitis C virus (HCV), human immunodeficiency virus
tuberculosis (TB) require a greater emphasis on infection prevention and control techniques.
Patients and their families need to be able to recognize sources of infection and
understand measures used to protect themselves. Patient teaching must include:
●basic information about infection
●the various modes of transmission
●appropriate methods of prevention (ex. hand hygiene, covering a cough)
Infection: the invasion of a susceptible host by pathogens or microorganisms, resulting in
disease.
Colonization: the presence and growth of microorganisms within a host but tissuewithout
invasion or damage
Communicable disease: an infectious disease which can be transmitted directly from one person
to another
Symptomatic disease: when pathogens multiply and cause clinical signs and symptoms
Asymptomatic disease: if clinical signs and symptoms are not present
*HCV is a communicable disease that can be asymptomatic (transmitted through direct
passage of blood into the skin from a percutaneous exposure)
Disease or infection results only if the pathogens multiply and alter normal tissue
function. Some infectious diseases (ex. ) have a low or no riskviral meningitis, pneumonia
for transmission so, although they are serious for patients, they don’t pose much risk for others.
Just because there’s a pathogen present, it does not mean that an infection will occur!
Infection occurs in a cycle that depends on the presence of these elements (in order):
1. an infectious agent or pathogen
2. a reservoir or source for pathogen growth
3. a port of exit from the reservoir
4. a mode of transmission
5. A port of entry to a host
6. A susceptible host
*Infection can develop if this chain remains uninterrupted. Preventing infections
involves breaking the chain of infection!
Microorganisms include bacteria, viruses, fungi, and protozoa.

Microorganisms on the skin are either resident or transient.
Resident flora: normal flora that are permanent residents of the skin and within the body, where
they survive and multiply without causing harm
The potential for microorganisms or parasites to cause disease depends on the number
present, their (ability to produce disease), their ability to enter and survive in a host,virulence
and the susceptibility of the host. Though resident flora are not virulent, these skin
microorganisms can cause serious infection when surgery or other invasive procedures allow
them to enter deep tissues or when a patient is severely (has an impairedimmunocompromised
immune system.
Transient flora: microorganisms that attach to the skin when a person has contact with another
person or object during normal activities (ex. When you touch a contaminated gauze dressing or
cleanse a patient following diarrheal episode).
If hands are visibly soiled, or care is being provided to a patient with Clostridium
difficile, washing with soap and water is the preferred practice. If hands are not visibly soiled,
use of an alcohol-based hand product or handwashing with soap and water is acceptable for
disinfecting hands of health care workers. Hand hygiene is the most effective way to break the
chain of infection!
Reservoir: a place where microorganisms survive, multiply, and await transfer to a susceptible
host (ex. animals, insects, food, water, fomites - organic material on inanimate surfaces). Human
reservoirs are divided into two types: those with acute or symptomatic disease and those who
show no signs of disease but are carriers of it. To thrive, organisms require a proper environment,
including appropriate food, oxygen, water, temperature, pH and light.
●Food - ex. (microbe that causes gas gangrene) thrives onClostridium perfringens
organic matter, consumes undigested foodstuff in the bowel, carbonEscherichia coli
dioxide and inorganic material (ex. soil) provide nourishment for other organisms
●Oxygen - aerobic bacteria (ex. ) causes more infections in humansStaphylococcus aureus
than anaerobic organisms and needs oxygen to survive. Anaerobic bacteria thrive where
little or no free oxygen is available (ex. In pleural cavity, joints, or in deep sinus tract).
An example of this is , a “normal flora organism” of the human colonBacteroides fragilis
that can cause infection if displaced into the bloodstream or surrounding tissue following
surgery or injury.
●Water - most organisms require water/moisture for survival (ex. moist drainage from a
surgical wound). Some bacteria form spores, which are resistant to drying and can live on
inanimate surfaces for long periods of time. An example of this is , which is anC. difficile
organism that causes antibiotic-induced diarrhea.
●Temperature - the ideal temperature for most human pathogens is 20° to 43° C (68° to
109° F). For ex. grows best in water at 25° to 42° C (77° toLegionella pneumophila
108° F). Cold temperatures tend to prevent growth and reproduction of bacteria
(bacteriostasis). A temperature or chemical that destroys bacteria is .bactericidal

●pH - the acidity of an environment determines the viability of microorganisms. Most of
them prefer an environment within a pH range of 5.0-7.0. Bacteria, in particular, thrive in
urine with an alkaline pH.
●Light - microorganisms like dark environments (ex. under dressings, in body cavities)
Portal of Exit: include sites such as blood, skin, mucous membranes, respiratory tract, and GI
tract. Some viruses such as are transmitted through direct contact with the blood or bodyEbola
fluids of a person who is sick with Ebola. However, droplets (ex. splashes or sprays) of
respiratory or other secretions from a person who is sick with Ebola could also be infectious.
Therefore, certain precautions (standard, contact, or droplet precautions) are recommended for
use in health care settings to prevent the transmission of the virus from patients who are sick
with Ebola to health care personnel and other patients/family members.
●Skin/Mucous membranes - any break in the skin and mucous membranes allows
pathogens to exit the body. This may be exhibited by the presence of purulent drainage.
●Respiratory Tract - pathogens that infect the respiratory tract (ex. influenza virus) are
released from the body when an infected person sneezes or coughs.
●Urinary Tract - normally, urine is sterile. But when a patient has a urinary tract
infection (UTI), microorganisms exit through urination.
●Gastrointestinal (GI) Tract - the mouth is one of the most bacterially contaminated
sites of the human body, but most of the organisms are normal floras. However,
organisms that are normal flora in one person can be pathogens in another (organisms
exit when a person expectorates saliva). Gastrointestinal portals of exit include emesis,
bowel elimination, drainage of bile via surgical wounds, or drainage tubes.
●Reproductive Tract - organisms such as and HIV exit through aNeisseia gonorrhea
man’s urethral meatus or a woman’s vaginal canal during sexual intercourse.
●Blood - the blood is normally a sterile body fluid, but in cases of communicable
diseases such as HBV, HCV, or HIV, it becomes a reservoir for pathogens. Organisms
exit from wounds, venipuncture sites, hematemesis, and bloody stool.
Modes of Transmission: each disease has a specific mode of transmission; by practicing
infection prevention and control techniques such as hand hygiene, you can interrupt the mode of
transmission! The same microorganism is sometimes transmitted by more than one route. For
example, varicella zoster (chickenpox) is spread by the airborne route in droplet nuclei or by
direct contact.
●Direct Contact - is person-to-person physical contact between the source and the
susceptible host (ex. touching patient feces and then touching your inner mouth,
consuming contaminated food)
○fecal-oral route
●Indirect Contact - personal contact of a susceptible host with a contaminated
inanimate object (ex. needles or sharp objects, dressings, environment)
Barrier protection - private room or cohort patients (see agency policy), gloves
and gowns

Infection/condition - VRE, MRSA, C. diff, shigella, and other enteric pathogens,
herpes simplex, scabies, varicella zoster (disseminated) etc.
●Droplet - large particles (>5 microns) that travel up to 3 feet during coughing,
sneezing, or talking that come in contact with a susceptible host
Barrier protection - private room or cohort patients; mask or respirator required
(depending on condition...refer to agency policy), gloves and gowns
Infection/condition - diphtheria (pharyngeal), rubella, pneumonia or scarlet fever
in infants and young children, mumps, etc.
●Airborne - droplet nuclei, residue, or evaporated droplets (<5 microns) suspended in
the air during coughing or sneezing, or carried on dust particles
Barrier protection - private room, negative-pressure airflow of at least 6-12
exchanges per hour via high-efficiency particulate air (HEPA) filtration; mask or
respiratory protection device, n95 respirator or PAPR (depending on condition),
gloves and gowns
Infection/condition - measles, chickenpox (varicella), disseminated varicella
zoster, pulmonary or laryngeal tuberculosis, TB, SARs
The major route of transmission for pathogens identified in the health care setting is
the unwashed hands of healthcare workers. Equipment used within the environment (ex.
stethoscope, blood pressure cuff, bedside commode) often becomes a source for the transmission
of pathogens.
Portal of Entry: Organisms enter the body through the same routes they use for exiting (ex during
venipuncture, organisms enter the body if proper skin preparation is not performed first). Factors
(such as a depressed immune system that reduce body defenses) can increase the risk of
pathogens entering the body.
Susceptible Host: Susceptibility (resistance) to an infectious agent depends on an individual's
degree of resistance to pathogens. A person's natural defenses against infection and certain
risk factors (ex, age, nutritional status, presence of chronic disease, trauma, smoking) affect
susceptibility. Organisms such as with resistance to key antibiotics are becoming moreS. aureus
common in all health care settings, acute care. Increased resistance is associated withespecially
frequent (and sometimes inappropriate) use of antibiotics over the years in all settings.
(FROM SLIDE)
Those most susceptible to disease are the very young (infants cannot control their
own airway), the poor, the uninsured, and those residing in areas where an infection is prevalent.
The Infectious Process
When a patient acquires an infection, you need to observe for signs and symptoms of
infection and take appropriate actions to prevent its spread. All infections follow a progressive
course.

1. Incubation Period - Interval between entrance of pathogen into body and appearance of
the first symptoms. : chickenpox (14 to 16 days after exposure), common coldExamples
(1 to 2 days), influenza (1 to 4 days), measles (10 to 12 days), mumps (16 to 18 days),
Ebola (2 to 21 days)
2. Prodromal Stage - Interval from onset of nonspecific signs and symptoms (ex. malaise,
low-grade fever, fatigue) to more specific symptoms. During this time microorganisms
grow and multiply, and patient may be capable of spreading disease to others. Example:
herpes simplex begins with itching and tingling at the site before the lesion appears
3. Illness Stage - Interval when patient manifests signs and symptoms specific to type of
infection. Examples: strep throat is manifested by a sore throat, pain, and swelling;
mumps is manifested by high fever, parotid and salivary gland swelling
4. Convalescence - Interval when acute symptoms of infection disappear. The length of
recovery depends on severity of infection and patient's host resistance; recovery may take
several days or months
Normal Flora: The use of broad-spectrum antibiotics for the treatment of infection can lead to
suprainfection (develops when broad-spectrum antibiotics eliminate a wide range of normal flora
organisms, not just those causing infection). When normal bacterial floras are eliminated, body
defenses are reduced, which allows disease-producing microorganisms to multiply, causing
illness
Body System Defenses: The skin, respiratory tract, and GI tract are easily accessible to
microorganisms. Pathogenic organisms can adhere to the surface skin, be inhaled into the lungs,
or be ingested with food. Each organ system has defense mechanisms physiologically suited to
its specific structure and function. For example, the lungs cannot completely control the entrance
of microorganisms. However, the airways are lined with moist mucous membranes and hairlike
projections, or cilia, that rhythmically beat to move mucus or cellular debris up to the pharynx to
be expelled through swallowing.
Inflammation - is the cellular response of the body to injury, infection, or irritation. It is a
protective vascular reaction that delivers fluid, blood products, and nutrients to an area of injury.
The process neutralizes and eliminates pathogens or dead (necrotic) tissues and establishes a
means of repairing body cells and tissues. Signs of localized inflammation include:
●swelling
●redness
●heat
●pain
●tenderness
●loss of function in the affected body part
Besides including vascular and cellular responses, the inflammatory response includes
formation of (fluid and cells that are discharged from cells or bloodinflammatory exudates
vessels such as pus or serum), and tissue repair.

Vascular and Cellular Responses - acute inflammation is an immediate response to cellular
injury. Rapid vasodilation occurs, allowing more blood near the location of the injury. The
increase in local blood flow causes the redness and localized warmth at the site of inflammation.
Injury causes tissue damage and possibly necrosis. As a result, the body releases chemical
mediators that increase the permeability of small blood vessels; and fluid, protein, and cells enter
interstitial spaces. The accumulation of fluid appears as localized swelling (edema). Another sign
of inflammation is pain, which is caused by the swelling of inflamed tissues that increases
pressure on nerve endings. As a result of the physiological inflammatory response, the involved
body part may have a temporary loss of function. For example, a localized infection of the hand
causes the fingers to become swollen, painful, and discolored. Joints become stiff as a result of
swelling, but function of the fingers returns when inflammation subsides.
Inflammatory Exudate - accumulation of fluid, dead tissue cells, and WBCs forms an exudate
at the site of inflammation. Exudate may be (clear, like plasma), (containingserous sanguineous
red blood cells), or (containing WBCs and bacteria). Usually the exudate is clearedpurulent
away through lymphatic drainage. Platelets and plasma proteins such as fibrinogen form a
meshlike matrix at the site of inflammation to prevent its spread.
Tissue Repair - when there is injury to tissue cells, healing involves the defensive, reconstructive,
and maturative stages. Damaged cells eventually are replaced with healthy new cells that
undergo a gradual maturation until they take on the same structural characteristics and
appearance as the previous cells. If inflammation is chronic, tissue defects sometimes fill with
fragile granulation tissue that eventually takes the form of a scar at the completion of the
healing process. The scar and surrounding tissues are not as strong as normal tissue and may be
more susceptible to injury from pressure, shear, or friction, which increases the risk for pressure
ulcer development
Healthcare–Associated Infections - patients in health care settings (especially hospitals and
long-term care facilities) have an increased risk of acquiring infections. HAIs result from the
delivery of health services in a healthcare facility. They occur as a result of:
●invasive procedures
●antibiotic administration
●the presence of multidrug-resistant organisms (MDROs)
●breaks in infection prevention and control activities
The number of health care employees having direct contact with a patient, the type and
number of invasive procedures, the therapy received, and the length of hospitalization influence
the risk of infection. Major sites for HAIs include:
●surgical or traumatic wounds
●urinary and respiratory tracts
●the bloodstream
HAIs significantly increase costs of health care. Older adults have increased susceptibility to
these infections because of their affinity to chronic disease and the aging process itself. Extended

stays in health care institutions, increased disability, increased costs of antibiotics, and prolonged
recovery times add to the expenses both of the patient and the health care institution and funding
bodies (ex. Medicare).
Costs for HAIs are often not reimbursed. As a result, prevention has a beneficial financial
impact and is an important part of managed care. Several national safety goals that focuses on
the care of older adults are: ensuring that older adults receive influenza and pneumonia vaccines,
and preventing infection after surgery.
HAI infections are either exogenous or .endogenous
Exogenous infections - come from microorganisms found outside the individual (ex. Salmonella,
Clostridium tetani, Aspergillus) and do not exist as normal flora.
Endogenous infections - occurs when part of the patient's flora becomes altered and an
overgrowth results (ex. staphylococci, enterococci, yeasts, and streptococci). This often happens
when a patient receives broad-spectrum antibiotics that alter the normal flora.
Iatrogenic infections - a type of HAI caused by an invasive diagnostic or therapeutic procedure.
For example, procedures such as bronchoscopy and treatment with broad-spectrum antibiotics
increase the risk for certain infections
Factors contributing to susceptibility:
●age
●nutritional status
●stress
●disease process
When care continues into the patient's home, the home care nurse plans to ensure that
the home environment supports good infection prevention and control practices. For example, if
a patient does not have running water yet requires wound care, even simple hand hygiene with
soap and water is difficult to achieve. Home health nurses instruct patients to perform hand
hygiene with either bottled water and soap or alcohol-based hand products.
Aproper diet helps the immune system function and consists of a variety of foods
from all food groups
Personal hygiene reduces microorganisms on the skin and maintain the integrity of
mucous membranes such as the mouth and vagina. Patients and family caregivers need to
understand techniques for cleansing the skin and how to avoid spread of microorganisms in body
secretions or excretions (ex. teach female patients how to wash their perineum from clean to
dirty, from the urethra down toward the rectum, using a clean washcloth with each wipe).
Immunization programs for infants and children have decreased the occurrence of
childhood diphtheria, whooping cough, and measles.
Adequate rest regular exerciseand help prevent infection.

Acute Care: Treatment of an infectious process includes eliminating the infectious organisms
and supporting a patient's defenses. To identify the causative organisms, you will collect
specimens of body fluids such as sputum or drainage from infected body sites for cultures. When
the disease process or causative organism is identified, the health care provider prescribes the
most effective treatment (e.g., antimicrobials).
Systemic infections require measures to prevent complications of fever (see Chapter
30). Maintaining intake of fluids prevents dehydration resulting from diaphoresis.
Medical Asepsis - the absence of pathogenic (disease-producing) microorganisms. Aseptic
technique refers to the practices/procedures that help reduce the risk for infection. The two types
of aseptic technique are asepsis. Basic medical aseptic techniques break themedical and surgical
chain of infection (use these techniques for all patients, even when no infection is diagnosed).
Aggressive preventive measures are highly effective in reducing HAIs. Hand hygiene, barrier
techniques, and routine environmental cleaning are examples of medical asepsis. Principles of
medical asepsis are also commonly followed in the home (ex. performing hand hygiene with
soap and water before preparing food, after using the bathroom, and after touching “dirty”
objects). It is important to include cultural or social beliefs of the patient and family.
Disinfection and sterilization use both physical and chemical processes that disrupt the internal
functioning of microorganisms by destroying cell proteins.
Disinfection - describes a process that eliminates many or all microorganisms, with the exception
of bacterial spores, from inanimate objects. There are two types of disinfection: (1) the
disinfection of surfaces, and (2) high-level disinfection, which is required for some patient care
items such as endoscopes and bronchoscopes.
Sterilization - eliminates or destroys all forms of microbial life, including spores. Sterilization
methods include processing items using steam, dry heat, hydrogen peroxide plasma, or ethylene
oxide (ETO).
The following factors influence the efficacy of the disinfecting or sterilizing method:
●concentration of solution and duration of contact
●type and number of pathogens
●surface areas to treat
●temperature of the environment
○room temperature is best!
●presence of soap
○soap causes certain disinfectants to be ineffective; thorough rinsing of an object is
necessary before disinfecting)
●presence of organic materials
○disinfectants become inactivated unless blood, ssaliva, pus, or body excretions are
washed off

Communication
(Giddens Ch.45)
Communication - a process of interaction between people in which symbols are used to create,
exchange, and interpret messages about ideas, emotions, and mind states
●Linguistic - spoken words and written symbols (verbal)
●Paralinguistic - gestures, eye contact, facial expressions (nonverbal)
●Metacommunication - context of the message
Process of Complementary Exchange - each person is either a sender or a receiver
Context - is important to the quality of meaning derived by participants during the process of
complementary exchange
●Factors include characteristics of the environment, relationship of participants (mutuality),
internal mood states (anxiety, etc.), mental and physical conditions, experience and
education, external noise, culture etc.
●Relationships
always
affect the communication process. In hierarchical relationships, power
and status affect communication between participants
Communication Competence - nurse must communicate
effectively
and
appropriately
with patients
and their family members, and other nurses and members of the healthcare team
*patient advocacy, assertiveness with peers when necessary, autonomy,
responsibility, use of patient’s name!
Patient Safety and Health Care Quality - communication is a frequently cited cause of error. Patient
safety requires effective communication. If you do this, you will have improved patient outcomes and
increased satisfaction with your patients!
*approx. 98,000 medical errors/year that lead to patient injury
Electronic Health Record - an accurate and timely documentation in the patient record that serves as
an important source of info
●is a major means of communication between members of the team
●is a legal document
●is evidence of provider’s actions (“if you don't record it, it didn’t happen”)
*don’t give your code to anyone!
Therapeutic communication techniques
●sharing empathy & feelings
●sharing hope
●sharing humor
●using touch
●using silence

*Assertive vs. Therapeutic vs. Intrapersonal vs. Interpersonal Communication
*Handoff/Reporting - when nurses communicate and share data with one another about their
patients via end-of-shift (or end-of-day) report
Critical thinking - helps nurses overcome perceptual biases or stereotypes that interfere with
accurately perceiving and interpreting messages from others. People often incorrectly assume
that they understand an individual's culture.
Communication Throughout the Nursing Process
●assessment (think )health history
●nursing diagnosis
●planning
●implementation
●evaluation
Facial Expressions - Consider the impact a nurse's facial expression has on a person who asks,
“Am I going to die?” The slightest change in the eyes, lips, or facial muscles reveals the nurse's
feelings. Although it is hard to control all facial expressions, try to avoid showing shock, disgust,
dismay, or other distressing reactions in a patient's presence.
Eye Contact - People signal readiness to communicate through eye contact. Maintaining eye
contact during conversation shows respect and willingness to listen. It also allows people to
closely observe one another. Lack of eye contact may indicate anxiety, defensiveness,
discomfort, or lack of confidence in communicating. However, people from some cultures
consider eye contact intrusive, threatening, or harmful and minimize or avoid its use. Always
consider a person's culture when interpreting the meaning of eye contact.
Eye movements communicate feelings and emotions. Looking down on a person establishes
authority, whereas interacting at the same eye level indicates equality in the relationship. Rising
to the same eye level as an angry person helps establish autonomy.
Sounds - Sounds such as sighs, moans, groans, or sobs also communicate feelings and
thoughts. Combined with other nonverbal communication, sounds help to send clear messages.
They have several interpretations: moaning conveys pleasure or suffering; and crying
communicates happiness, sadness, or anger. Validate nonverbal messages with patients to
interpret them accurately.
Territoriality and Personal Space - During interpersonal interaction people maintain varying
distances between one another depending on their culture, the nature of their relationship, and the
situation. When personal space becomes threatened people respond defensively & communicate
less effectively. Situations dictate whether the interpersonal distance between nurse and patient is
appropriate. Nurses frequently move into patients' territory and personal space because of the

nature of caregiving. You need to convey confidence, gentleness, and respect for privacy,
especially when your actions require intimate contact or involve a patient's vulnerable zone.
Phases of the Helping Relationship
●Pre-Interaction Phase (before meeting a patient)
○Review available data, including the medical and nursing history.
○Talk to other caregivers who have information about the patient.
○Anticipate health concerns or issues that arise.
○Identify a location and setting that fosters comfortable, private interaction.
○Plan enough time for the initial interaction.
●Orientation Phase (when the nurse and patient meet and get to know one another)
○Set the tone for the relationship by adopting a warm, empathetic, caring manner.
○Recognize that the initial relationship is often superficial, uncertain, and tentative.
○Expect the patient to test your competence and commitment.
○Closely observe the patient and expect to be closely observed by the patient.
○Begin to make inferences and form judgments about patient messages and
behaviors.
○Assess the patient's health status.
○Prioritize the patient's problems and identify his or her goals.
○Clarify the patient's and your roles.
○Form contracts with the patient that specify who will do what.
○Let the patient know when to expect the relationship to be terminated.
●Working Phase (when the nurse and patient work together to solve problems and
accomplish goals)
○Encourage and help the patient express feelings about his or her health.
○Encourage and help the patient with self-exploration.
○Provide information needed to understand and change behavior.
○Encourage and help the patient set goals.
○Take action to meet the goals set with the patient.
○Use therapeutic communication skills to facilitate successful interactions.
○Use appropriate self-disclosure and confrontation.
●Termination Phase (during the ending of the relationship)
○Remind the patient that termination is near.
○Evaluate goal achievement with the patient.
○Reminisce about the relationship with the patient.
○Separate from the patient by relinquishing responsibility for his or her care.
○Achieve a smooth transition for the patient to other caregivers as needed.
Common courtesy is part of professional communication. To practice courtesy, say hello and
goodbye to patients and knock on doors before entering. State your purpose, address people by
name, and say “please” and “thank you” to team members. Introduce yourself and state your
title. When a nurse is discourteous, others perceive him or her as rude or insensitive. It sets up
barriers to forming helping relationships between nurse and patient and causes friction among
team members.

Always introduce yourself. Failure to give your name and status (e.g., nursing student, RN, or
licensed practical nurse) or acknowledge a patient creates uncertainty about an interaction and
conveys an impersonal lack of commitment or caring. Making eye contact and smiling recognize
others. Addressing people by name conveys respect for human dignity and uniqueness. Because
using last names is respectful in most cultures, nurses usually use a patient's last name in an
initial interaction and then use the first name if the patient requests it. Ask how your patients and
co-workers prefer to be addressed and honor their personal preferences.
Trusting another person involves risk and vulnerability; but it also fosters open, therapeutic
communication and enhances the expression of feelings, thoughts, and needs. Without atrust
nurse-patient relationship rarely progresses beyond social interaction and superficial care. Avoid
dishonesty at all costs. Withholding key information, lying, or distorting the truth violates both
legal and ethical standards of practice. Sharing personal information or gossiping about others
sends the message that you cannot be trusted and damages interpersonal relationships.
It is especially important to assess the psychophysiological factors that influence
communication. Many altered health states and human responses limit communication. People
with hearing or visual impairments often have difficulty receiving messages. Facial trauma,
laryngeal cancer, or endotracheal intubation often prevents movement of air past vocal cords or
mobility of the tongue, resulting in inability to articulate words. An extremely breathless person
needs to use oxygen to breathe rather than speak. People with aphasia after a stroke or in
late-stage Alzheimer's disease cannot understand or form words. Some mental illnesses such as
psychosis or depression cause patients to jump from one topic to another, constantly verbalizing
the same words or phrases or exhibiting a slowed speech pattern. People with high anxiety are
sometimes unable to perceive environmental stimuli or hear explanations. Finally, patients who
are unresponsive or heavily sedated cannot send or respond to verbal messages. Patients who are
unable to speak are at risk for injury unless nurses identify an alternate communication method.
Review of a patient's medical record provides relevant information about his or her ability to
communicate. The medical history and physical examination document physical barriers to
speech, neurological deficits, and pathophysiology affecting hearing or vision.
Tips for Improved Communication with Older Adults Who Have Hearing Loss
●Make sure the patient knows that you are talking.
●Face the patient, be sure that your face/mouth is visible to him or her, and do not chew
gum or talk while chewing.
●Speak clearly but do not exaggerate lip movement or shout.
●Speak a little more slowly but not excessively slow.
●Check if patient uses hearing aids, glasses, or other adaptive equipment.
●Choose a quiet, well-lit environment with minimal distractions.
●Allow time for the patient to respond. Do not assume that patient is being uncooperative
if he or she does not reply or takes a long time to reply.
●Give the patient a chance to ask questions.
●Keep communication short and to the point. Ask one question at a time.

Sociocultural Factors - Culture influences thinking, feeling, behaving, and communicating.
Be aware of the typical patterns of interaction that characterize various ethnic groups, but do not
allow this information to bias your response. Know each patient individually (ex. does he or she
feel comfortable with eye contact or in sharing information with others?). You will approach a
patient very differently if he or she is open and willing to discuss private family matters versus
others who are reluctant to reveal personal or family information to strangers.
Foreign-born people do not always speak or understand English. Those who speak English
as a second language often experience difficulty with self-expression or language
comprehension. To practice cultural sensitivity in communication, understand that people of
different ethnic origins use different degrees of eye contact, personal space, gestures, loud voice,
pace of speech, touch, silence, and meaning of language. Make a conscious effort not to interpret
messages through your cultural perspective, but consider the communication within the context
of the other individual's background. Avoid stereotyping, patronizing, or making fun of other
cultures. Language and cultural barriers are not only frustrating but also dangerous, causing
delay in care.
Active listening means being attentive to what a patient is saying both verbally and
nonverbally.
Empathy is the ability to understand and accept another person's reality, accurately perceive
feelings, and communicate this understanding to the other.
Appropriate encouragement and positive feedback are important in fostering hope and
self-confidence and for helping people achieve their potential and reach their goals. You give
hope by commenting on the positive aspects of the other person's behavior, performance, or
response. Sharing a vision of the future and reminding others of their resources and strengths
also strengthens . Reassure patients that there are many kinds of hope and that meaning andhope
personal growth can come from illness experiences. For example, a nurse says to a patient
discouraged about a poor prognosis, “I believe that you'll find a way to face your situation
because I've seen your courage and creativity.”
Humor is an important but often underused resource in nursing interactions. It is a coping
strategy that can reduce anxiety and promote positive feelings. It is a perception and attitude in
which a person can experience joy even when facing difficult times.
Today it is common to care for patients from different cultural backgrounds. When you
interact with patients be sensitive and realize that they may misunderstand or misinterpret jokes
and statements meant to be humorous. For example, a person who is homosexual might not
appreciate a joke with sexual orientation, or a person from a lower socioeconomic group is not
likely to enjoy a joke that disparages a minority.
Health care professionals sometimes use a kind of after difficult ordark, negative humor
traumatic situations as a way to deal with unbearable tension and stress. This coping humor has a
high potential for misinterpretation as uncaring by people not involved in the situation. For

example, nursing students are sometimes offended and wonder how staff are able to laugh and
joke after unsuccessful resuscitation efforts. When nurses use coping humor within earshot of
patients or their loved ones, great emotional distress results.
Feelings are not right, wrong, good, or bad, although they are pleasant or unpleasant.
Touch is one of the most potent and personal forms of communication. It expresses concern
or caring to establish a feeling of connection and promote healing. Touch conveys many
messages such as affection, emotional support, encouragement, tenderness, and personal
attention. Comfort touch such as holding a hand is especially important for vulnerable patients
who are experiencing severe illness with its accompanying physical and emotional losses. BE
SENSITIVE to others’ reactions to touch and use it wisely! Always ask permission.
It takes time and experience to become comfortable with . Most people have a naturalsilence
tendency to fill the empty spaces with words, but sometimes these spaces really allow time for a
nurse and patient to observe one another, sort out feelings, think about how to say things, and
consider what has been communicated. Silence prompts some people to talk. It allows a patient
to think and gain insight.
Providing relevant information tells other people what they need or want to know so they are
able to make decisions, experience less anxiety, and feel safe and secure.
To check whether you understand a message accurately, an unclear or ambiguousrestate
message to clarify the sender's meaning.
Focusing involves centering a conversation on key elements or concepts of a message. If
conversation is vague/rambling/repetitive, focusing is a useful technique. Don’t use this if it
interrupts patients when they’re discussing important issues. Rather, use it to guide the direction
of conversation to important areas.“We've talked a lot about your medications; now let's look
more closely at the trouble you're having in taking them on time.”
Paraphrasing is restating another's message more briefly using one's own words.
Validation is a technique that nurses use to recognize and acknowledge a patient's thoughts,
feelings, and needs. Patients and families know they are being heard and taken seriously when
the caregiver addresses their issues. For example, a nurse validates the patient's stated comments
by asking, “Tell me if I understand your concerns regarding your surgery. You're worried that
you will not be able to return to your usual way of life.” This type of statement enables a nurse to
convey empathy and interest in the patient's thoughts, feelings, and perceptions.
Ask only one question at a time and fully explore one topic before moving to another area.
Summarizing is a concise review of key aspects of an interaction. It brings a sense of
satisfaction and closure to an individual conversation and is especially helpful during the
termination phase of a nurse-patient relationship. By reviewing a conversation, participants focus
on key issues and add relevant information as needed.
Self-disclosure - This is not a therapy for a nurse; rather it shows a patient that the nurse
understands his experiences and that they are not unique. You choose to share experiences or
feelings that are similar to those of the patient and emphasize both the similarities and
differences.
Confrontation - When you confront someone in a therapeutic way, you help the other person
become more aware of inconsistencies in his or her feelings, attitudes, beliefs, and behaviors
(Stuart, 2013). This technique improves patient self-awareness and helps him or her recognize
growth and deal with important issues. Use confrontation only after you have established trust,
and do it gently with sensitivity: “You say you've already decided what to do; yet you're still
talking a lot about your options.”
Asking personal questions that are not relevant to a situation simply to satisfy your curiosity
is not appropriate professional communication.
When a nurse gives a personal opinion, it takes decision making away from the other person.
Changing the subject when another person is trying to communicate his or her story is rude
and shows a lack of empathy.
Making stereotypical remarks about others reflects poor nursing judgment and threatens
nurse-patient or team relationships.
False Reassurance -“Don't worry, everything will be alright.” When a patient is seriously ill or
distressed, you may be tempted to offer hope to him or her with statements such as “You'll be
fine” or “There's nothing to worry about.” When a patient is reaching for understanding, false
reassurance discourages open communication. Offering reassurance not supported by facts or
based in reality does more harm than good. Although you are trying to be kind, it has the
secondary effect of helping you avoid the other person's distress, and it tends to block
conversation and discourage further expression of feelings. A more facilitative response is, “It
must be difficult not to know what the surgeon will find. What can I do to help?”
Sympathy is a subjective look at another person's world that prevents a clear perspective of
the issues confronting that person. If a nurse over-identifies with a patient, objectivity is lost, and
the nurse is not able to help the patient work through the situation.
Asking for Explanations -“Why are you so anxious?” Some nurses are tempted to ask patients
why they believe, feel, or act in a certain way. Patients frequently interpret “why” questions as
accusations or think nurses know the reasons and are simply testing them. Regardless of a
patient's perception of your motivation, asking “why” questions causes resentment, insecurity,
and mistrust. If you need additional information, it is best to phrase a question to avoid using the

word “why.” For example, “You seem upset. What's on your mind?” is more likely to help an
anxious patient communicate.
Approval or Disapproval - “You shouldn't even think about assisted suicide; it's not right.” Do
not impose your own attitudes, values, beliefs, and moral standards on others while in the
professional helping role. Other people have the right to be themselves and make their own
decisions. Judgmental responses often contain terms such as should, ought, good, bad, right, or
wrong. Agreeing or disagreeing sends the subtle message that you have the right to make value
judgments about patient decisions. Approving implies that the behavior being praised is the only
acceptable one. Often a patient shares a decision with you, not in an effort to seek approval but to
provide a means to discuss feelings. Disapproval implies that the patient needs to meet your
expectations or standards. Instead help patients explore their own beliefs and decisions. The
response, “I'm surprised you're considering assisted suicide. Tell me more about it,” gives the
patient a chance to express ideas or feelings without fear of being judged.
Becoming defensive in the face of criticism implies that the other person has no right to an
opinion. The sender's concerns are ignored when the nurse focuses on the need for self-defense,
defense of the health care team, or defense of others.
Passive or Aggressive Responses - Nurses who lack assertive skills also use triangulation
(i.e., complaining to a third party rather than confronting the problem or expressing concerns
directly to the source). This and draws others into the conflict situation.lowers team morale
Assertive communication is a far more professional approach for a nurse to take.
Challenging or against perceptions denies that they are real and valid. Resolvearguing
conflicts; don’t start them.
General Survey/Vital Signs/Pain (Summary)
Two-Step BP - mainly used on new patients (baseline value)
Temp, pulse, respiratory rate, bp and oxygen ( )order of vital signs
Pulse
●Indicator of circulatory status
●Electrical impulses from the sinoatrial (SA) node
●Use of stethoscope
○Bell (abnormal, low pitch)
○Diaphragm (normal, high pitch)
●Character of the pulse (rate, rhythm, strength, quality)
●Children have pulse“abnormal”
○faster when breathing in
○slower when breathing out
●Tachycardia (>100 beats/min) vs. Bradycardia (<60 beats/min)
○2+ is regular strength pulse (0 is no pulse, 4 is very strong pulse)
○Factors influencing pulse = exercise, fever, medications, anxiety
Normal Pulse (beats/min)
●Infant: 120-160
●Toddler: 90-140
●Preschooler: 75-100
●School-age child: 60-90
●Adolescent: 60-100
Respiratory Rate
●Respiration
○Ventilation - movement of gases into/out of the lung
○Diffusion - movement of oxygen & carbon monoxide between alveoli and RBCs
○Perfusion - distribution of RBCs to/from the pulmonary capillaries
○Physiological control; hypoxemia
●Easy to assess
○respiratory rate: breaths/minute
○ventilatory depth: deep, normal, shallow
○ventilatory rhythm: regular/irregular
●Normal range: “generally” breaths per minute12-20
○children have a higher respiratory rate
Normal Respiratory Rate
●Newborn: 30-60
●Infant: 30-50
●Toddler (2 years): 25-32
●Child: 20-30
●Adolescent:16-20
●Adult: 12-20
Temperature
●Heat produced - heat loss = body temp.
●Acceptable temperature range
○96.8 degrees F to 100.4 degrees F
○36 degrees C to 38 degrees C
●Newborns (anything over 100.4 - newborns are very sensitive tocall the doctor
environmental conditions because their )hypothalamus is immature
●Rectal temperatures are generally 5 degrees C (9 degrees F) higher than oral temp.
●For the elderly, their temperature is on the cooler side. They have a hard time keeping
warm due to aged hypothalamus
●Factors affecting temperature include age, exercise, hormone levels, time of day, stress,
etc. Temperature alterations (brought about by the environment) include hypothermia and
heat stroke
Advantages and Disadvantages of Select Temperature Measurement Sites (on phone)
Hypothermia? Remove wet clothes and keep warm
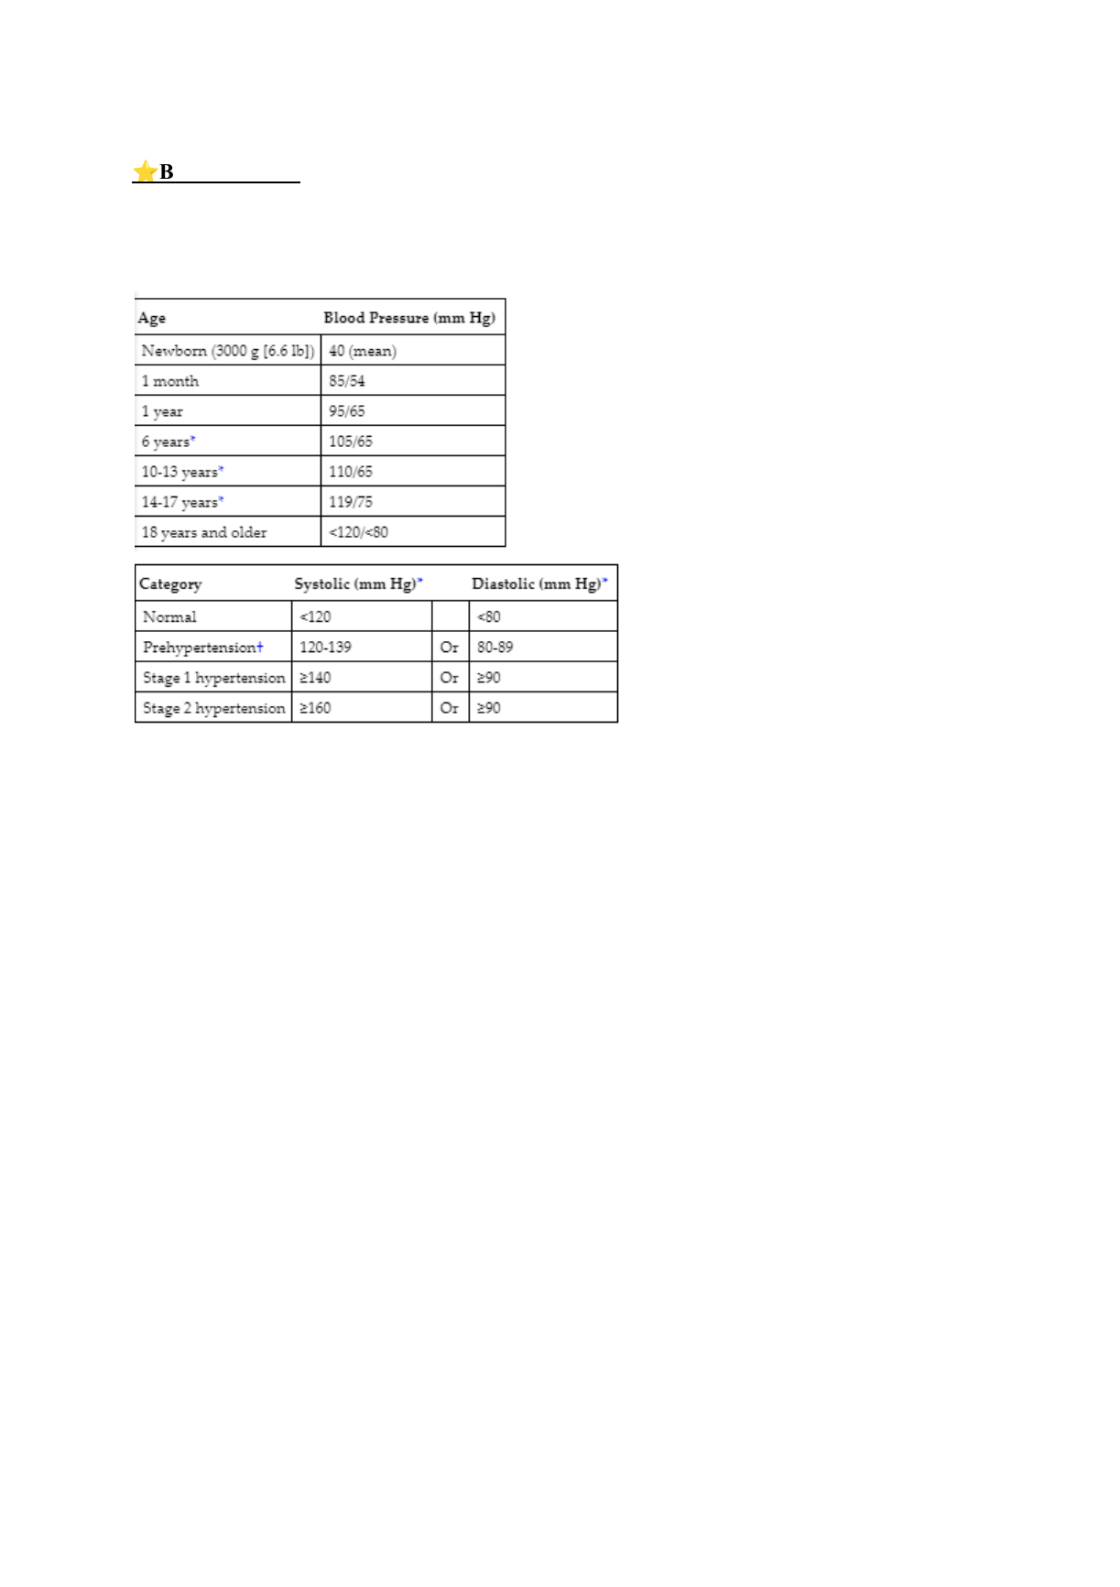
Blood Pressure
●force exerted on the walls of an artery by pulsing blood under pressure from the heart
○Systolic = max. peak pressure during ventricular contraction
○Diastolic = min. pressure during ventricular relaxation
●Pulse pressure = Difference between systolic and diastolic
Arteriosclerosis (hardening of the blood vessels)
●Influencing factors: age, stress, daily variation, ethnicity, gender, smoking
Hypertension (high blood pressure)
●more common than hypotension
●thickening of walls & loss of elasticity
●family history (*genetics)
●risk factors
Hypotension (low blood pressure)
●systolic <90 mmHg
○Some “petite individuals” may have a systolic bp of a little less than 90. Look at other
vital signs before documenting this as their “normal” baseline value.
●dilation of arteries & loss of blood volume
●decrease of blood flow to vital organs
●orthostatic/postural
○when bp changes from sitting to standing position (vise versa)
Most likely to fail them
Adults: heart
Infants: respiratory system

Oxygen: 95% or above
P = Provocation/Palliation
What were you doing when the pain started? What caused it? What makes it better or worse?
Q = Quality/Quantity
What does it feel like? Use words to describe the pain such as sharp, dull, stabbing, burning,
crushing, throbbing, nauseating, shooting, twisting or stretching.
R = Region/Radiation
Where is the pain located? Does the pain radiate? Where? Does it feel like it travels/moves
around? Did it start elsewhere and is now localized to one spot?
S = Severity Scale
How severe is the pain on a scale of 0 to 10, with zero being no pain and 10 being the worst pain
ever? Does it interfere with activities? How bad is it at its worst? Does it force you to sit down,
lie down, slow down? How long does an episode last?
T = Timing
When/at what time did the pain start? How long did it last? How often does it occur: hourly?
daily? weekly? monthly? Is it sudden or gradual? What were you doing when you first
experienced it? When do you usually experience it?

