


1
Chapter 1: Introduction to the Study
To obtain optimal patient outcomes, nurses need to reason clinically and make
sound clinical judgments (Dickson et al., 2018; Jessee, 2018; Tyo & McCurry, 2019).
The ability to recognize changes in patients’ conditions, perform timely and appropriate
patient assessments, analyze data, and make sound clinical judgments are key to the
successful transition from nursing school into clinical practice (Tyo and McCurry, 2019).
However, nurse educators are not consistent in fostering the knowledge, skills, and
attitudes necessary to effectively practice in a complex healthcare environment as many
new graduate nurses are not practice ready, especially when it comes to clinical
judgments (Parker et al., 2014). Tyo and McCurry (2019) noted a significant problem for
academia is a gap in the literature identifying educational strategies that are effective in
the development of clinical reasoning. Furthermore, I also identified few educational
strategies that were effective in the development of clinical reasoning in nursing students.
Desiring to make graduate nurses more practice ready with an increase in clinical
reasoning skills, nurse educators at a small community college in the southeastern United
States were willing to try different educational strategies to assist in the development of
clinical reasoning skills. While the educational intervention of questioning was
implemented at the site, no one had evaluated the strategy for effectiveness.
Implementing educational strategies without empirical evidence on their effectiveness in
the development of clinical reasoning left the educators guessing if the strategies would
be effective. By developing and testing a range of evidenced-based teaching/learning
strategies that assist in the development of clinical reasoning, a systematic approach to

2
clinical reasoning could be embedded in nursing programs curricula, easing new nurse
graduates’ transition into practice (Parker et al., 2014). This addition of evidenced-based
teaching/learning strategies will add currency to the knowledge base of nursing
education. Stevens (2013) also concurred that teaching strategies used by nurse educators
should be based on sound evidence.
Nurse educators are challenged to shift their emphasis on critical thinking to
clinical reasoning as they prepare nurses to care for more complex patient problems
commonly seen in healthcare today (Benner et al., 2010). This shift in nursing education
allows graduate nurses to consider the what-if questions by using creative, critical,
scientific, and critical thinking to make sound clinical decisions. However, few studies
have investigated specific teaching/learning strategies to assist in the development of
clinical reasoning in nursing students. The topic of this study was to evaluate the
influence of questioning as a problem-based teaching/learning strategy on the
development of clinical reasoning in undergraduate nursing students.
The vision of Walden University is working to foster social change through
research, practice, and the education of motivated scholar-practitioners (Walden
University, 2017). This study may evoke positive social change by influencing nursing
students, nursing faculty, patients, and healthcare providers. In addition, the results of this
study may increase evidenced-based knowledge concerning learning strategies to
promote clinical reasoning in nursing students allowing them to make better clinical
judgments as they transition into practice. Facilitating the development of clinical
reasoning in nursing students is critical to achieving desirable patient outcomes.

3
Chapter 1 will cover the background of the problem, the problem statement, the
purpose of the study, the research question and hypotheses, the theoretical framework for
the study, and the nature of the study. In addition, I will include a definition of terms, my
assumptions, and the scope and delimitations of the study. Any limitations identified will
be discussed as will the significance of the study.
Background
Healthcare partners in a community in the southeastern United States identified a
problem with new graduates not being practice ready, specifically presenting with limited
clinical reasoning skills. Through a search of the literature, it was identified that this
problem was not specific to the southeastern United States. Instead, various studies
identified a widening preparation-to-practice gap with a focus on clinical reasoning
(Gonzalez, 2018; Kavanagh & Szweda, 2017; Silvestre et al., 2017; Tyo & McCurry,
2019). Educators in the small community college where this study took place set out to
identify educational strategies that could assist students in the development of clinical
reasoning skills.
Merisier et al. (2018) posited that problem-based learning (PBL) has been
implemented successfully as a learning strategy to promote clinical reasoning in other
healthcare fields. PBL is a strategy developed in the late 1960s at the McMaster
University Medical School in Hamilton, Ontario, Canada (Jones, 2008). This PBL
strategy utilizes active and self-directed learning to promote analytical reasoning,
communication, and team problem-solving skills (Jones, 2008). Problems provide the
foundation for discussions rather than traditional lecture driven classrooms, developing

4
problem solving skills for real life problems (Breytenbach et al., 2017). PBL would assist
nursing students in the ability to ask those what-if questions using a variety of ways of
thinking and reasoning as they make clinical judgments.
Merisier et al. (2018) concluded that determining the most effective strategies to
develop clinical reasoning was key to a safe and successful transition into practice. While
researching teaching/learning strategies that were most effective in facilitating clinical
reasoning, I found few studies that focused on specific teaching/learning strategies in the
development of clinical reasoning in nursing students (Breytenbach et al., 2017). Of the
studies identified, most were on outcome measures that were questionnaires, self-
reporting surveys, transcript analysis, verbal analysis, and exams or tests (Burbach et al.,
2015; Chan, 2014; Harmon & Thompson, 2015; Jessee & Tanner, 2016). Many of these
studies described by Breytenbach et al. and Tyo and McCurry were over 8 years old,
were tested in BSN programs, and used a mixture of methodologies to include
quantitative, qualitative, and mixed-methodology (Breytenbach et al., 2017; Tyo and
McCurry, 2019). The use of case studies as an educational strategy was evaluated by
exam, questionnaires, transcript analysis, direct observation, and self-reporting surveys in
several studies (Carvalho& Oliveria, 2011; Dawson et al., 2014; Russell et al., 2011).
Reflective journaling, another strategy studied by Murphy (2004), supported the
development of clinical reasoning. Other educational strategies studied in the
development of clinical reasoning included clinical coaching (Jessee & Tanner, 2016),
collaborative learning (Harmon & Thompson, 2016), and several studies evaluated the
use experiential or clinical practicum (Kubin et al., 2013). Another evaluated method is

5
the use of the outcome present state test by Kautz et al. (2006). Even with the extensive
research on teaching strategies for the development of clinical reasoning in prelicensure
nursing students, graduate nurses continue to fall short in clinical reasoning skills making
them less than practice ready to handle the complex healthcare issues of today. More
teaching strategies need to be investigated.
I launched a quantitative study examining the effect of questioning as a
teaching/learning strategy in an associate degree nursing program. Evidence-based
knowledge on the educational strategy of questioning was not found in my review of the
literature and is therefore recognized as a gap in knowledge. For this study, I identified
the influence that questioning had on the development of clinical reasoning, adding to the
knowledge base of teaching/learning strategies in the development of clinical reasoning
among nursing students.
Problem Statement
Clinical reasoning is the basis for every decision made by nurses and with sound
clinical reasoning skills, a positive impact on patient outcomes is possible (Merisier et al.,
2018). Academic programs have a commitment to develop and assist students to graduate
with the skills, knowledge, and abilities to provide safe, competent care (Kavanagh &
Szweda, 2017). The NCLEX (National Council Licensing Examination) pass rate has
been the standard by which most programs are evaluated. However, graduate nurses who
passed NCLEX continue to the workforce without the confidence and clinical reasoning
skills needed to make sound clinical judgments in today’s healthcare (Kavanagh &
Szweda, 2017). Only 23% of newly graduated nurses are safely able to recognize

6
problems due to urgent changes in patient condition and demonstrate appropriate
management of those problems (Kavanagh & Szweda, 2017). The National Council of
State Boards of Nursing ([NCSBN]; 2019) stated that while knowledge is essential, there
was not enough evidence to show that nurses possessed the clinical judgment essential
for safe nursing practice with the current NCLEX. NCSBN is currently undertaking a
radical transformation of the NCLEX to assess higher-order thinking. Dickison (as cited
in NCSBN, 2019) posited that the overall goal of assessing if a nursing candidate is
minimally competent is a public protection issue.
Nurses with sound clinical reasoning skills have a positive impact on patient
outcomes (Billings & Halstead, 2016), conversely, comparatively poor reasoning skills
may result in adverse patient outcomes (Benner, 2015; Tyo & McCurry, 2019). New
graduate nurses have reported that the development of clinical reasoning was critical to
the basis of their ability to recognize cues and prevent failure to rescue (Herron, 2017).
Yet, most new graduates are not practice ready, especially when it comes to making
sound clinical judgments (Parker et al., 2014). Having graduate nurses who are not
practice ready presents a quality and safety issue for healthcare. Harmon and Thompson
(2015) concluded that it is essential to foster clinical reasoning in order to provide safe,
effective nursing care. The complexity of healthcare today does not afford the luxury of
developing clinical reasoning after graduation, requiring graduate nurses to effectively
reason and make sound clinical judgments sooner than later (Herron, 2017). This places
the emphasis on the development of clinical reasoning skills on nursing programs. New
graduates are stressed by the expectations that they perform like a nurse with 20 years of

7
experience (Parker et al., 2014). This stress leads new nurse graduates to perceive
themselves as unsafe practitioners in certain situations (Parker, et al., 2014).
Clinical reasoning and judgment are essential end of program outcomes for
prelicensure nursing students (Bussard, 2018; Tyo & McCurry, 2019). With the
increasing complexity of patient problems, nursing graduates must be able to adjust
quickly to a patient’s changing needs (Carvalho, et al., 2017). Being able to
systematically analyze the situation and develop a solution is key to safe, quality
healthcare. Teaching nursing students how to reason clinically will develop nurses who
can adjust and problem solve in changing patient situations. Providing nurse educators
with evidenced-based learning strategies for the development of clinical reasoning skills
will help future nurses provide safe, quality care.
Nurse educators need evidenced-based strategies that will enable them to foster
the development of nursing students capable of meeting complex healthcare needs
(Jessee, 2018). Nurse educators are challenged to develop learning/teaching strategies
and experience that would foster the development of clinical reasoning in nursing
students (Harmon & Thompson, 2015). Determining the most effective strategies to
develop clinical reasoning in nursing education is key to graduate nurse’ successful
transition into clinical practice and the achievement of desired patient outcomes
(Carvalho, et al., 2017; Merisier et al., 2018; Tyo & McCurry, 2019). While researching
teaching/learning strategies effective in the development of clinical reasoning, I found the
following strategies studied: case studies and clinical scenarios, web-based case studies,
case studies or clinical scenarios with structured model or theory, clinical coaching,

8
collaborative learning, concept mapping, experiential or clinical practicum, reflective
journaling, and simulation. PBL has been implemented as a teaching/learning strategy to
promote clinical reasoning in many healthcare fields (Barrows, 1996; Macarthur &
Dwyer, 1989). Few studies have investigated the effects of specific PBL strategies on
clinical reasoning (Harmon & Thompson, 2015; Jessee & Tanner, 2016).
Studies concerning PBL strategies involve the influence on critical thinking, not
clinical reasoning, in nursing (Merisier et al., 2018). Carvalho et al. (2017) identified
PBL as the most commonly used teaching intervention for critical thinking. The
development and testing of teaching/learning strategies to foster the development of
clinical reasoning in nursing students is in response to the challenge delivered by Harmon
and Thompson (2015) to nurse educators.
Wosinski et al. (2018) posited that the goal of PBL is to improve clinical
reasoning skills. They further noted that clinical reasoning fostered by PBL increased
self-efficacy in:
• self-learning
• the use of clinical reasoning pathways
• solving of clinical problems
• transferring skills to clinical practice
• building knowledge as a team
• developing leadership skills.
Questioning is one of the most frequently used PBL strategies in raising a student’s
cognitive ability (Gilkison, 2003). Merisier et al. (2018) reasoned that questioning, as a

9
PBL teaching strategy, would influence clinical decision making. While it appears that
the use of questioning influences clinical reasoning, there is no empirical evidence to
support the assumption (Merisier et al., 2018).
The problem identified is two-fold. First, new nurse graduates are not practice
ready when it comes to clinical reasoning and clinical judgment (Bussard, 2018; Herron,
2017; Jessee & Tanner, 2016; Parker et al., 2014). Nurses who are not able to clinically
reason are more likely to make poor clinical judgments, leading to poor patient outcomes.
A new graduate who enters the workforce with developed clinical judgment and
reasoning skills can ensure safe, quality, and effective care in healthcare settings
(Bussard, 2018). The second problem identified is a noted gap in the literature in
identifying what educational strategies are effective in the promotion of higher-level
thinking in nursing such as clinical reasoning (Tyo & McCurry, 2019). None of the
identified strategies included PBL, even though PBL has been used in the development of
clinical reasoning in other health related fields such as medicine (Barrows & Tamblyn,
1980; Barrows, 1986: Merisier et al., 2018). Because other healthcare disciplines use
PBL in the development of clinical reasoning, I conducted additional research on
questioning, the most used PBL strategy, in the development of clinical reasoning in
prelicensure nursing students.
Purpose of the Study
The purpose of this study was to investigate the influence of questioning as a PBL
strategy on clinical reasoning in prelicensure nursing students using secondary data from
a nursing program from 2017-2019. PBL is one of the most widely used learning methods

10
to foster clinical reasoning (Merisier, et al., 2018). Because questioning is the most
prominent PBL strategy, the use of questioning has important implications for nursing
education in the investigation of effective learning strategies to development clinical
reasoning in undergraduate nursing students. In this study, I provided empirical evidence
on the use of questioning in the development of clinical reasoning in nursing students by
comparing the pre and post questioning evaluations using the Lasater clinical judgment
rubric. This study used a retrospective quantitative approach, with deidentified data from
the records of nursing students enrolled in their last lower-level clinical course, who were
required to participate in simulation experiences as a portion of their clinical experiences
for the specified clinical course. Data analysis examined the influence of questioning, the
independent variable, on clinical reasoning, the dependent variable using a paired t test.
Research Question and Hypotheses
Research Question (RQ)-Quantitative: To what extent does the use of questioning as a
problem-based learning strategy influence the development of clinical reasoning in
prelicensure nursing students?
H0: Questioning as a problem-based strategy has no influence on the development
of clinical reasoning in prelicensure nursing students.
Ha: Questioning as a problem-based strategy influences the development of
clinical reasoning in prelicensure nursing students.
The variables were measured using the Lasater Clinical Judgment Rubric (Lasater, 2007).
Paired t test analysis was conducted using SPSS to evaluate the difference in the levels of
clinical reasoning before and after the intervention of questioning was implemented. The

11
paired t test was used because there is one group being evaluated with pre and
postintervention evaluation. G* Power 3.1.94 was used to calculate a prior sample size
for selection of data to include in the analysis (Faul et al, 2007). Data was secondary data
provided by a small community college in the southeastern United States from students in
their last clinical lower-level course from the years 2017-2019.
Theoretical Framework
The theoretical framework used to guide this study was Tanner’s clinical
judgment model. Tanner’s clinical judgment model consists of four components:
noticing, interpreting, responding, and reflecting (Tanner, 2006). Noticing is the
perceived judgment of the situation: What are the nurse’s expectations of the situation?
Expectations are based on the nurse’s knowledge of the patient in determining if this a
normal pattern of response for the patient. Expectations are also based on the nurse’s
knowledge and previous experiences. Interpreting is the process that allows the nurse to
grasp the situation and begin using reasoning to make sense of the data. This allows the
nurse to determine if more data is needed to interpret the situation accurately. By
interpreting the meaning of the data, the nurse then determines an appropriate plan of
action or the response to the situation. Responding is the plan of action developed by the
interpretation of the data or may be either intuitive or implied. This response must be
evaluated for effectiveness. Reflecting, the last component of the clinical judgment
model, is accomplished by one of two methods: reflection-in-action and reflection-on-
action. Reflection-in-action is interpreting the patient’s response to the action taken.
Reflection-on-action is taking a step back and reflecting about what was learn from this

12
situation. This ongoing learning from reflection contributes to the nurse’s clinical
judgment and their ability to take this knowledge and apply it to future clinical
judgments.
Clinical reasoning is evident in all components of the clinical judgment model.
Tanner (2006) defined clinical judgment as an “interpretation of the patient’s needs,
concerns, or health problems and the decision to take action” and clinical reasoning as
“the process by which nurses and other clinicians make their judgments” (p. 204). This
approach details how nurses think and the clinical reasoning behind their judgments.
Tanner’s clinical judgment model was chosen for this study due to the clarity and
ease of use of the model. I chose the Lasater clinical judgment rubric (LCJR) as my
measurement tool due to its alignment with Tanner’s clinical judgment model. Lasater’s
clinical judgment rubric consists of 11 areas for evaluation within the four components of
the clinical judgment model. Effective noticing is evaluated with focused observation,
recognizing deviations from expected patterns, and information seeking. Effective
interpreting involves prioritizing data and making sense of the data. Effective responding
involves a calm manner in which the situation is approached, clear communication, well
planned interventions to include flexibility in response, and skill. Last, effective
reflecting involves self-analysis and a commitment to improvement.
This theory aligns well with the research topic of the influence of questioning on
the development of clinical reasoning in nursing students. The clinical judgment model
through LCJR provides an opportunity to evaluate questioning on the development of
clinical reasoning. Clinical reasoning is the process a nurse uses to make a clinical

13
judgment. The four aspects or dimensions of noticing, interpreting, intervening, and
reflection lends itself to evaluation of the process of clinical reasoning.
Nature of the Study
A quantitative, comparative study using a one group ex post facto design with
secondary data was selected to provide a means of testing for improvement in clinical
reasoning after a new method was implemented (Creswell, 2014). Identified variables
included the independent variable of questioning and the dependent variable of clinical
reasoning. Variables were measured by the LCJR by assigning a numerical value to the
11 components of the rubric. This instrument allows the evaluator to assign a total score
for clinical judgment and reasoning using the students level of expertise of each
component. The level of expertise ranged from beginning (1 point) to exemplary (4
points). The student’s clinical judgment and reasoning was evaluated based on secondary
data obtained before and after questioning using the LCJR. Data was analyzed using a
paired t test. For this study, I used a quantitative one group pre/postintervention approach
to investigate the difference between the preintervention clinical reasoning score and the
postintervention clinical reasoning score following the intervention of questioning.
The simulation experience that was the foundation for the data used for this
retrospective study included a series of questions designed to encourage a deeper thought
process. The simulation was a required clinical component of the nursing program.
Clinical reasoning is the thought process that healthcare professionals use to make
clinical judgments (Vallente, 2016, p. 1). The quasi-experimental one group ex post facto
design will be used to examine the retrospective data (Grove et al., 2013). The quasi-

14
experimental design is less rigorous than an experimental design that uses a randomized
sampling and a control group. The student data was obtained from student records from a
small community college in the southeastern United States. The students engaged in the
simulation and then were evaluated prequestioning by using a clinical judgment tool.
Following the guided questions, the students repeated the simulation and were
reevaluated postquestioning using the same clinical judgment tool.
The clinical judgment tool was developed by the college using the components of
Lasater’s clinical judgment rubric. The students’ work, at that time, were evaluated by
their simulation faculty as satisfactory or unsatisfactory. I used the LCJR to quantitatively
evaluate the students’ work. The LCJR is a grading tool that describes the students’ levels
of performance in clinical judgment, focusing on the process of clinical reasoning
(Lasater, 2007). Keeping the focus on clinical reasoning remains consistent with Tanner’s
(2006) components of noticing, interpreting, responding, and reflecting and can easily be
evaluated using the LCJR due to its close alignment with the clinical judgment model
(Lasater, 2007).
Operational Definitions
The following terms were used throughout the study. Listed below are the
definitions of the terms.
Clinical judgment is defined as “an interpretation or conclusion about a patient’s
needs, concerns, or health problems, and/or the decision to take action (or not), use or
modify standard approaches, or improvise new ones as deemed appropriately by the
patient’s response; (Tanner, 2006, p. 204)

15
Clinical reasoning is “the thought process by which healthcare professionals
gather and analyze patient information, evaluate the relevance of the data, and identify
potential actions that could improve the physiological and psychosocial conditions of
patient under their care" (Vallente, 2016, p. 1).
Critical thinking is “the ability to apply higher-order cognitive skills
(conceptualization, analysis, evaluation) and the disposition to be deliberate about
thinking (being open-minded or intellectually honest) that lead to action that is logical
and appropriate (p. 716).
Cues are changes experienced by the patient, either physiological or
psychological (Levett-Jones et al., 2010). The nurse perceives these changes through
history and/or assessment based on knowledge and beliefs.
Interpreting is the making sense of what has been noticed by ruling out
hypotheses until the interpretation supports the data noticed and collected (Tanner, 2006).
This is the second component of Tanner’s clinical judgment model.
Learning strategies are the methods students use to learn (Instructional Design,
n.d.)
Noticing the perceived judgment of the situation (Tanner, 2006). This is the first
component of the Tanner’s clinical judgment model.
Nurse educators refers to the faculty who facilitate learning in undergraduate
nursing courses.
Nursing students for this study are defined as prelicensure undergraduate nursing
students.

16
Practice-ready refers to the possession of “skill proficiencies and competencies to
be able to assume the responsibilities of a professional nurse following graduation and
passing the NCLEX [National Council of Licensure Examination]” (Harmon &
Thompson, 2015).
Problem-based learning is a learning strategy introduced in the late 1960s and is
defined as the “learning that results from the process of working toward the
understanding or resolution of a problem” (Barrows & Tamblyn, 1980, p. 18).
Questioning is defined as an “interrogative expression often used to test
knowledge” or the “act or instance of asking” (Merriam-Webster, n.d.).
Reflecting is the fourth component of Tanner’s clinical judgment model.
Reflection is a self-evaluation of action and an evaluation of the situation with the
intention of increasing knowledge and clinical judgment skills for the future (Tanner,
2006).
Responding is the third component of Tanner’s clinical judgment model.
Responding is the chosen action taken based on the nurse’s interpretation of the situation
(Tanner, 2006).
Teaching/learning strategies are defined as “the structure, system, methods,
techniques, procedures and processes that a teacher uses during instruction” (NW
Missouri, 2018).
Assumptions
Things that are believed to be true are assumptions and are not necessarily under
the control of the researcher (Nieswiadomy & Bailey, 2018; Simon, 2011). Assumptions

17
may be implied from theory or research, universal assumptions, or common sense. For
this study, I am making the following assumptions.
• Clinical reasoning affects patient outcomes (Harmon & Thompson, 2015; Jessee,
2018); Merisier et al., 2018; Vallente, 2016). Based on this assumption from
previous studies, clinical reasoning becomes an appropriate variable in the study.
• Clinical reasoning should be taught in undergraduate nursing programs. Bussard
(2018) stated in her study the importance of new graduate nurses entering the
workforce being prepared to handle complex patient situations in order to ensure
safe, quality, and effective patient care.
• Nurse educators should use evidenced-based teaching/learning strategies
(Breytenbach et al., 2017). This assumption is the basis of all research on
teaching/learning strategies. This study will increase the evidence-based strategies
that influence clinical reasoning.
• Nursing students can be taught how to reason clinically (Breytenbach et al., 2017;
deCarvalho et al., 2017; Tyo & McCurry, 2019). This assumption is well
supported by research as noted above. Teaching nursing students how to use
various types of thinking in the development of clinical reasoning will facilitate
sound clinical judgments, resulting in better outcomes for patients (Harmon &
Thompson, 2015).
• I assumed that participants provided their best responses on the clinical judgment
tools based on the fact that the data was part of a required clinical experience.

18
Scope and Delimitations
I investigated the influence of questioning on clinical reasoning in prelicensure
nursing students. Larue (2008) posited that PBL was shown to be favorable in the
development of clinical reasoning skills. The choice of questioning as the
teaching/learning strategy to be investigated was based on questioning being the most
prominently used PBL strategy (Merisier et al., 2018). The use of questioning has
important implications for nursing education with the investigation of effective
teaching/learning strategies in undergraduate nursing students.
The scope or boundaries of the study were a convenience sampling of community
college undergraduate nursing students from an associate degree nursing (ADN) program
in the southeastern United States. The majority of the studies published on clinical
reasoning teaching strategies from 1998 to 2016 were from baccalaureate nursing
programs, while only two were from the community college setting (Tyo & McCurry,
2019). None of these studies investigated questioning as an education strategy (Tyo &
McCurry, 2019). Inclusion criteria for this study included undergraduate nursing students
in the same course with the same simulation experience. One researcher evaluated the
data retrospectively to ensure consistency of the grading. Exclusion criteria included
students from disciplines other than nursing and students who were not prelicensure
nursing students.
While Tanner’s clinical judgment model was selected as the theoretical
framework for this study, other potential frameworks were considered. The National
Council of State Boards of nursing clinical judgment model was considered. This model

19
encompasses three of the leading clinical judgment models: Tanner’s clinical judgment
model, dual process reasoning theory, and the information processing model (Dickison et
al., 2018). This is a multilayered clinical judgment model that forms, defines, and
evaluates hypotheses. This model did not lend itself to studying questioning as a
teaching/learning strategy as easily as Tanner’s clinical judgment model. The dual
process reasoning theory was also considered. This theory set its roots in Hammond’s
cognitive continuum theory (1978). Hammond (1978) describe clinical judgment as an
adaptive strategy lying between intuitive and analytical thinking. This theory aligned well
but was difficult to align with a measurement tool. Also considered was the NLN/Jeffries
simulation model. It was discarded due to the measurement tool evaluating students’
perceptions instead of assessing development of students’ clinical judgment.
The quasi-experimental design is less rigorous than an experimental design due to
the use of a convenience sampling. This method of nonrandom sampling limits the
probability that each element of the population will be included in the sample
(Nieswiadomy & Bailey, 2018). Generalizations are restricted with this sampling method.
Limitations
There are three limitations identified with this study. The first is the use of a
convenience sample which does not allow for the study to be generalized to a larger
population (Simon, 2011). This sample may not be a true representation of all
prelicensure nursing students in a variety of settings and circumstances (Creswell, 2014).
The second limitation is that there is no way of knowing if clinical reasoning was
impacted by previous knowledge, experience, or skills. The whole cohort was used to

20
help minimize the risk of statistical regression since students’ knowledge, skills, and
experiences are varied. The comparison of pretest and posttest evaluation data allowed
for a determination of growth in clinical reasoning based on the use of questioning
regardless of their starting point. This sample represented nursing students in a small
community college and may not be representative of larger populations. Replication of
this study in other types of prelicensure nursing programs, such as a diploma or BSN
program, would address this limitation.
Another limitation was time. This study evaluated retrospective data from nursing
students in one semester, with a pre and postevaluation of the intervention of questioning.
This snapshot in time is dependent upon conditions at that time. All students were given
material to prep them for the simulation to ensure that all student has a solid knowledge
base prior to the simulation.
Using data collected on multiple small groups throughout the semester could
present a problem with contamination of the data. However, to allow all students the
opportunity for the same experiences in simulation lab, students were required by the
college to sign a confidentiality agreement to not discuss simulations outside of Sim Lab.
While I had no control on the conditions in which the secondary data was collected, I am
reasonably confident that the college’s standards were maintained. I will be the sole
evaluator of the retrospective data to ensure consistency of grading.
Significance of the Study
In a scoping review of the literature, Merisier et al. (2018) were unable to find any
evaluation of the influence of questioning on the development of clinical reasoning. I also

21
completed a thorough review of the literature and was unable to find any evaluation of
the influence of questioning on clinical reasoning to corroborate questioning as an
effective strategy in the development of clinical reasoning. Breytenbach et al. (2017)
concluded in their integrative literature review on the best available literature on
evidenced-based teaching strategies for nurse educators was very limited, recommending
that researchers investigate the best use of teaching strategies. This current study
provided empirical evidence on the use of questioning as a PBL strategy in the
development of clinical reasoning in nursing students. This study assisted in filling the
gap in the literature on effective educational strategies for the development of clinical
reasoning in nursing students.
This study may evoke positive social change by influencing nursing students,
nursing faculty, patients, and healthcare providers. This study increases evidenced-based
knowledge concerning learning strategies to promote clinical reasoning in nursing
students allowing them to make better clinical judgments as they transition into practice.
Facilitating the development of clinical reasoning in nursing students is critical to
achieving desirable patient outcomes. Students need to become more comfortable with
changing patient conditions, recognizing cues, considering patient and family concerns,
and using sound clinical reasoning to intervene as necessary. Students with sound clinical
reasoning skills are more practice ready, have more confidence, and transition as new
graduates into practice more easily (Parker, et al., 2014).
This study, by increasing the knowledge of evidenced-based teaching/learning
strategies, has significant implications for social change. The use of evidence-based

22
teaching/learning strategies give nurse educators the tools to effectively impact the
knowledge, skills, and attitudes in development of clinical reasoning in nursing students.
The complexity of healthcare today does not afford nursing the luxury of developing
clinical reasoning after graduation, as suggested by Herron (2017). Herron (2017) posited
that new graduate nurses felt that the development of clinical reasoning was critical as it
was the basis of their ability to recognize and prevent failure to rescue.
Nurse educators should adopt learning strategies that are evidenced-based
(Breytenbach et al., 2017). There is a need for evidenced-based strategies that will
develop nursing students capable of meeting complex healthcare needs. Evidenced-based
learning strategies will allow for better curriculum development.
Having a nurse who can rapidly identify changes in conditions and respond
appropriately and timely will improve patient outcomes. Lives depend on a nurses’
ability to make sound clinical judgements, making this a priority competency in nursing
education. Failure to identify and interpret cues in a timely manner can lead to
devastating consequences for the patient. Robeznieks (2015) reports that the New York-
based Jonas Center for Nursing Excellence estimates that each nurse educator has the
potential to affect the care of 3.6 million patients. This number is based on the number of
nurses each instructor could teach along with the number of patients for whom those
nurses could provide care (Robeznieks, 2015). Improving the clinical reasoning skills of
nursing students truly effects millions of patients. Better patient outcomes will have the
potential to reduce inpatient length of stay with more efficient care. More efficient care
can potentially lend to a saving of resources and dollars for healthcare in general.

23
Practice-ready new graduates have the potential to decrease orientation costs of
new graduates. The readiness of new graduates to enter the workforce is an international
concern creating not only the necessity of longer orientation programs, but many
hospitals have added extended residency programs for new graduate support (Baumann et
al., 2017; Parker et al., 2014).
Summary and Transition
The problem that motivated this research was the insufficiency of practice ready
graduate nurses capable of handling the complex patient problems experienced in
healthcare today, especially related to clinical judgments. Clinical reasoning is the
process nurses use to make sound clinical judgments. The rationale for choosing this
problem was the challenge made to nurse educators for the development of
teaching/learning strategies that would foster clinical reasoning in nursing students by
Herron and Thompson (2015). In other healthcare fields, PBL is a frequently used
educational strategy for the development of clinical reasoning. However, there is little
research on individual PBL strategies (Breytenbach et al., 2017). Questioning was
selected as the teaching/learning strategy to research within the theoretical framework of
Tanner’s clinical judgment model.
The study used a quantitative approach consistent with determining the cause-
and-effect relationships between the independent variable “questioning” and the
dependent variable “clinical reasoning.” Key terms relative to the problem were
identified, as well as assumptions, scope, delimitations, and limitations. The significance

24
of the study was emphasized as well as its impact on social change. The literature review
will be discussed in Chapter 2.

25
Chapter 2: Literature Review
Nurse educators should shift emphasis on critical thinking to clinical reasoning as
they prepare nurses to handle the complex patient problems likely to be encountered in
today’s healthcare (Benner et al., 2010). Benner et al (2010) posited that nurses need
multiple ways of thinking, including clinical reasoning with the use of clinical
imagination. Benner et al. (2010) defined clinical reasoning as the “ability to reason as a
clinical situation change, taking into account the context and concerns of the patient and
family” (Benner et al., 2010, p. 85). This shift in nursing education allows graduate
nurses to consider the what-if questions by using creative, critical, scientific, and thinking
to make sound clinical decisions. However, few studies have investigated specific
teaching/learning strategies to assist in the development of clinical reasoning in nursing
students.
This literature review was a detailed summary of (a) the influence of PBL on
clinical reasoning and clinical judgment, (b) problem-based teaching/learning strategies
utilized in developing clinical reasoning and clinical judgment in nursing students, (c) the
need to develop clinical reasoning skills in nursing students, and (d) the conceptual
frameworks of Tanner’s clinical judgment model and Lasater’s clinical judgment tool and
rubric. After discussing my search strategies, including databases accessed and key terms
used, I reviewed the theoretical framework used, Tanner’s clinical judgment model
(Figure 1). The main portion of this chapter is the literature review is where I addressed
the following concepts: clinical reasoning/clinical judgment, PBL, and
questioning/inquiry.
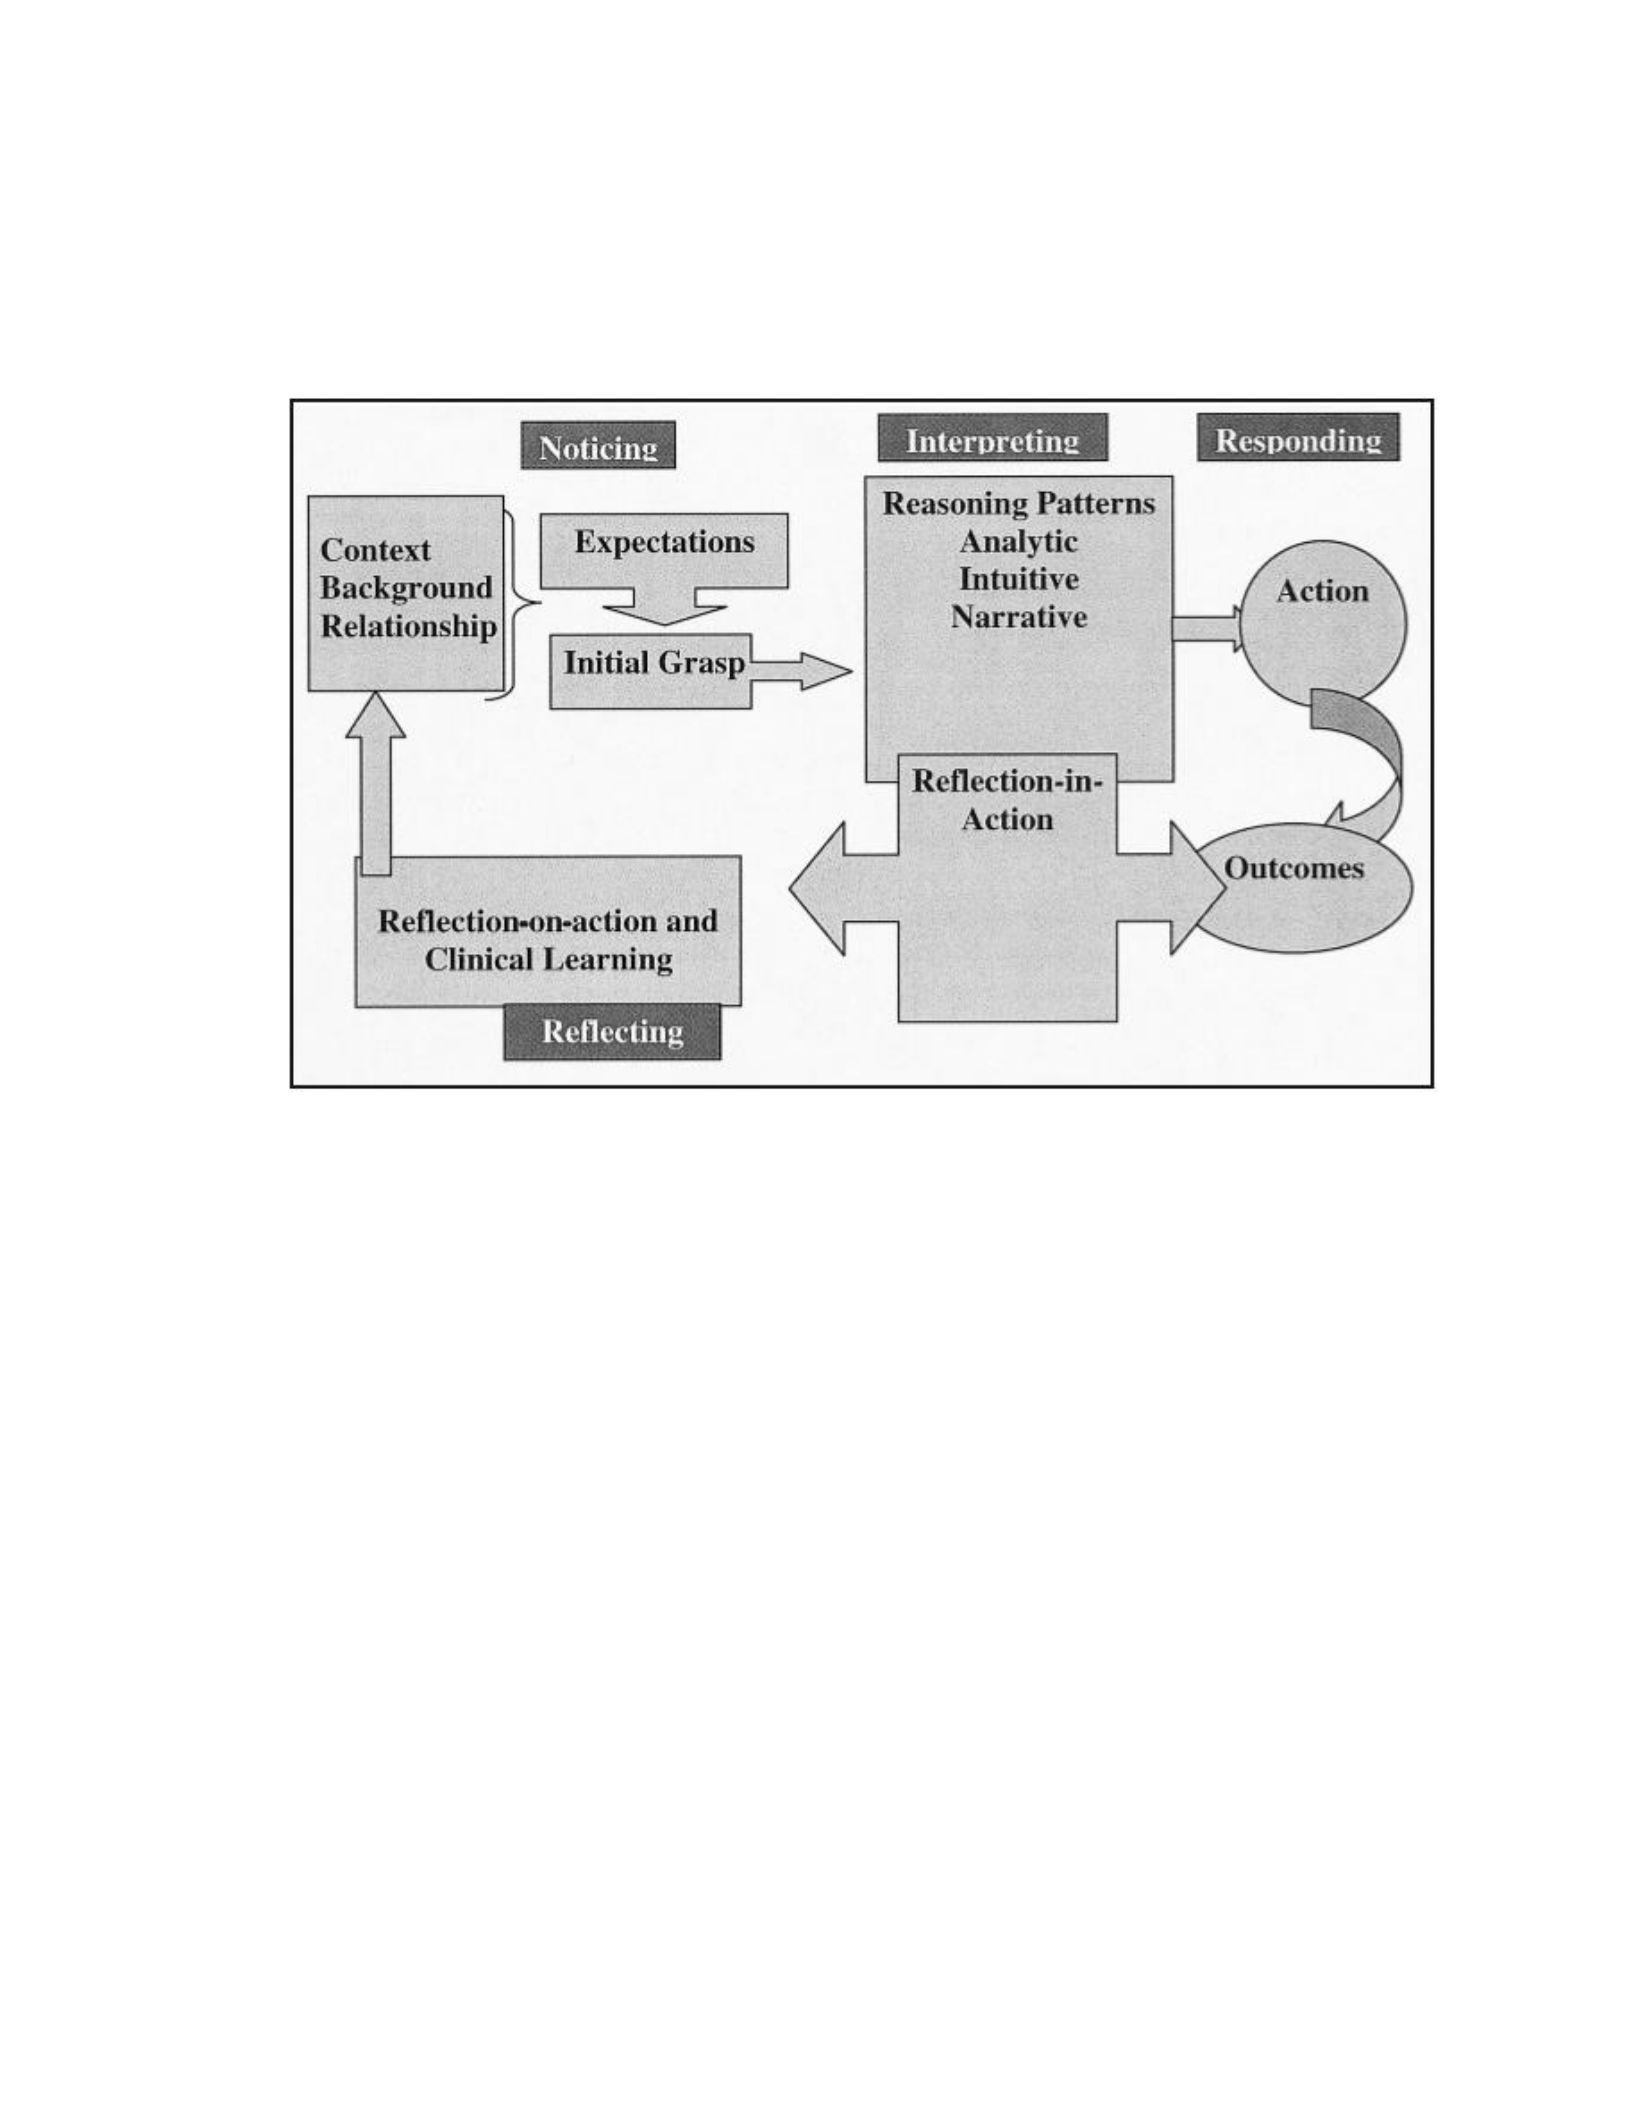
26
Figure 1
Tanner’s Clinical Judgment Model
Note. Tanner’s Clinical Judgment model depicting the four components of noticing,
interpreting, responding, and reflecting. Adapted from “Thinking Like a Nurse: A
Researched-Based Model of Clinical Judgment in Nursing” by C. A. Tanner, 2006,
Journal of Nursing Education, 45(6), p. 208.
Literature Search Strategies
I searched nursing and education databases to identify articles relative to the
development of clinical reasoning. Inclusion criteria for the literature review included
studies from the discipline of nursing, prelicensure nurses, PBL, questioning/inquiry, and
educational strategies that were specific to clinical reasoning. Studies were excluded if
they were (a) not empirical, (b) conference abstracts, (c) dissertation papers, (d) written in

27
a language other than English, (e) did not include prelicensure nurses and (f) were
deemed irrelevant in contributing to the research questions. The databases used included
CINAHL, MEDLINE, OVID, and EBSCO, ProQuest Nursing, and ERIC. Key search
terms included clinical reasoning, clinical judgment, nursing education, learning
strategies, teaching strategies, problem-based learning, questioning, inquiry, Tanner’s
Clinical Judgment Model, and Lasater’s Clinical Judgment Rubric. Boolean searches
included the following combinations: clinical reasoning OR clinical judgment AND
nursing education AND learning strategies; clinical reasoning OR clinical judgment
AND nursing education AND problem-based learning; problem-based learning AND
learning OR teaching strategies AND clinical judgment OR clinical reasoning; clinical
reasoning OR clinical judgment AND nursing education AND questioning OR inquiry.
The terms that yielded the greatest results were clinical reasoning, clinical judgment,
problem-based learning, and nursing education. Tanner’s clinical judgment model and
Lasater’s clinical judgment rubric were added the search as a possible theoretical model
and tool for measuring clinical judgment for the research.
The scope of the literature review was limited to the years between 2013 and
2019. The literature searches were conducted using the Walden University online library,
online nursing and health professional journals, textbooks, and various nursing websites.
The literature search continued until saturation was met. This was determined when
search items yielded repetitive results among the databases.
Included are the seminal works of Barrows (1986) and Barrows and Tamblyn
(1980) on PBL in the review. Other seminal works included were Tanner’s (2006)

28
clinical judgment model, Lasater’s (2007) clinical judgment rubric. Educating Nurses: A
Call for Radical Transformation (Benner et al., 2010) was also included due to the
frequency of reference in various studies as a driving force to move from critical thinking
to clinical reasoning in the development of nurses.
Theoretical Foundation
Tanner’s clinical judgment model is the foundation for many studies on clinical
reasoning and clinical judgment (Ashley & Stamp, 2014: Bussard, 2015; Jessee &
Tanner, 2016; Monagle, Lasater, Stoyles, & Dieckmann, 2018). Tanner (2006) developed
the clinical judgment model based on five general conclusions acquired from her review
of almost 200 studies concerning clinical judgment. These conclusions are: (1) nurses’
previous experience, background as well as objective data concerning the situation; (2)
knowing patients’ typical pattern of responses as well as patient engagement; (3) context
in which the situation occurred and the culture of the unit; (4) reasoning patterns used by
nurses; and (5) reflection on any breakdown of clinical reasoning to improve future
outcomes (Tanner, 2006).
It is important to define terms relevant to the clinical judgment model. Tanner
(2006) defines clinical judgment as “an interpretation or conclusion about a patient’s
needs, concerns or health problems, and/or the decision to take action (or not), use or
modify approaches, or improvise new ones as deemed appropriate by the patient’s
response” (p. 204). Tanner (2006) referred to the term clinical reasoning to describe the
processes nurses and other clinicians use to make clinical judgments. Tanner (2006)
describes these processes as a deliberate generation of alternatives, to include a

29
comparison to the evidence and choose what is most appropriate for the patient. This
process includes identifying patterns of practical reasoning, the recognition of patterns,
intuitive clinical grasp, and responding without evident forethought.
The clinical judgment model consists of four aspects based on a synthesis of the
literature on clinical judgment; noticing, interpreting, responding, and reflecting (Figure
1) Noticing is the perceived judgment of the situation. For example, to ascertain the
concept of noticing a researcher might ask whether the nurses’ expectations concerning
the patient condition being met or not? The nurses’ expectations are based on previous
experience of similar patients and/or situations, knowledge of the patient and their
patterns of responses, and knowledge from textbooks. Factors such as the nurses’ vision
of excellent care, nursing unit culture and patterns of care on the unit, nurses’ values
concerning the situation, and the work environment all have the potential to influence
what is noticed (Tanner, 2006). Interpreting, the second aspect of clinical judgment, is
the development of sufficient understanding to respond to the situation. This process uses
reasoning patterns to interpret the data, develop hypotheses that supports the data, and
determine an appropriate response. Responding is the chosen course of action to the
situation. The response may be a decision based on a deliberate reasoning process as
discussed above, or it may be intuitive where response to the intervention confirms the
action.
The final aspect of the clinical judgment model is reflecting. There are two parts
to this aspect. Reflection-in-action and reflection-on-action. Reflection-in-action refers to
the nurses’ ability to evaluate the patient and make adjustment to the course of action is

30
the desired outcomes are not being achieved. Reflection-on-action refers to the clinical
learning that the nurse gains from the experience.
Tanner’s clinical judgment model has been used as the theoretical framework for
studies on clinical judgment and clinical reasoning. Ashley and Stamp (2014) used
Tanner’s clinical judgment model to evaluate clinical judgment and reasoning skills of
nursing student in high-fidelity simulation. The study was qualitative in nature where
each student was interviewed individually after viewing the video of their performance
using a debriefing script tailored to the individual performances. The five themes that
emerged from this study were: (a) thinking like a nurse; (b) assessment depth; (c) looking
for answers to patient problem; (d) communication between healthcare team using SBAR
(Situation, Background, Assessment, and Recommendation), and (e) magical or reflective
thinking. Ashley and Stamp (2014) concluded that novice nursing students would benefit
from a pre-simulation conference to help in them think like a nurse. A pre-simulation
conference would allow for students to learn pertinent information concerning a
condition that could be applied in the reasoning process.
Bussard (2015) used the clinical judgment model as the framework for her
qualitative, interpretive study on the evaluation of the development of clinical judgment
in prelicensure nursing students through the use of reflection journals. Students went
through four high fidelity simulation scenarios and provided reflection journals with each
scenario. The Lasater clinical judgment rubric (LCJR) was used to evaluate the journal
entries as beginning, developing, accomplished, and exemplary. The LCJR is based on
the four aspects of the clinical judgment model. Bussard (2015) concluded that reflective

31
journaling is an effective teaching-learning strategy for prelicensure nursing students in
the development of clinical judgment. Other studies support the use of reflection or
reflective journaling as an effective educational strategy for the development of clinical
reasoning (Jessee & Tanner, 2016; Monagle et al., 2018).
Jessee and Tanner (2016) used a quantitative approach in the development of a
clinical coaching tool that used ono-on-one teaching, verbal questioning, and feedback
behaviors to improve clinical reasoning in nursing students. Tanner’s clinical judgment
model was used as the framework for the study. The significance of the study was the
tool, clinical coaching interactions inventory (CCII) advanced the measurement of
clinical coaching from qualitative to quantitative. The teaching-questioning dimension
were based on common clinical teaching strategies. The question examples followed
Bloom’s taxonomy and included remembering, understanding, analyzing, evaluating or
creating, along with reflective questions. While clinical coaching development was the
goal of this study, the use of questioning by the clinical coach was a desired component
of clinical coaching. The questions increased in complexity based on Bloom’s
Taxonomy, forcing a higher level of thinking. While this was not the focus of the study, it
is relevant to my study.
Monagle, Lasater, Stoyles, and Dieckmann (2018) used Tanner’s clinical
judgment model as the framework of their study to determine if structured reflection
exercises would produce a more practice-ready new graduate nurse. The study utilized a
mixed method approach, quantitative and qualitative. Three tools were used to evaluate
clinical judgment; the health sciences reasoning test, the clinical workplace learning

32
culture survey (validity of tool has yet to be determined), and the Lasater clinical
judgment rubric. The Lasater clinical judgment rubric is closely aligned with Tanner’s
clinical judgment model.
The LCJR has been used to provide feedback to students as they self-evaluate and
reflect on simulation and clinical experiences (Lasater, 2011). The rubric is based on the
four aspects of Tanner’s clinical judgment model: noticing, interpreting, responding, and
reflecting. Lasater (2011) posited that for effective noticing to take place, there must be a
focused observation, a recognition of any deviations from expected normal, and the
ability to recognize any additional information needed. The rubric emphasizes effective
interpreting as the involvement of making sense of the data and prioritizing data (Lasater,
2011). Effective responding involves a calm and confident manner of approach, the
exhibition of clear communication, a well-planned intervention that leaves room for
flexibility, and being skilled in nursing (Lasater, 2011). The last aspect of Tanner’s
clinical judgment model is reflection. The rubric identifies two areas of involvement,
self-analysis/evaluation and a commitment to improvement (Lasater, 2011). The rubric
evaluates each component on a four-point scale, with four being exemplary, three,
accomplished, two developing, and one beginning. This instrument will be used to scale
students’ performance in a simulation, first as the students’ initial evaluation and
secondly with guided questioning to help students deepen their understanding and
increase their clinical reasoning skills. The goal of the rubric is to help nursing students
think like a nurse.

33
Tanner’s clinical judgment model was chosen for this study due to the clarity and
ease of use of the model. I chose the LCJR as my measurement tool due to its alignment
with Tanner’s clinical judgment model. This theory aligns well with the research topic of
the influence of questioning on the development of clinical reasoning in nursing students
since clinical reasoning is the process used to make clinical judgments. The clinical
judgment model through LCJR provides an opportunity to evaluate questioning on the
development of clinical reasoning. Clinical reasoning is the process a nurse uses to make
a clinical judgment. The four aspects or dimensions of noticing, interpreting, intervening,
and reflection lends itself to evaluation of the process of clinical reasoning. Few studies
discuss learning strategies for nursing educators to employ in the development of clinical
reasoning. Most of the studies that are available, discuss reflective journaling as a
learning strategy (Ashley & Stamp, 2014; Bussard, 2015; Monagle et al., 2018).
Literature Review Related to Key Variables and/or Concepts
This review provides a detailed summary of the literature regarding the influence
of problem-based learning strategies, specifically questioning, on the development of
clinical reasoning in undergraduate nursing students. The review includes studies related
to learning strategies in the development clinical reasoning in nursing students. In
addition, a section is provided to discuss the strengths and weaknesses of past research
approaches. After providing a rationale for the selection of variables, the review of the
literature is divided into three sections relative to the key variables of the study; clinical
reasoning/clinical judgment, problem-based learning, and questioning/inquiry.

34
Related Studies: Interests and Methodologies
Patients’ outcomes depend on nurses’ abilities to reason clinically to make sound
clinical judgments (Dickson et al, 2018; Jessee, 2018; Tyo & McCurry, 2019). Parker,
Giles, Lantry, and McMillan (2014) posited that most new graduate nurses are not
practice ready, especially when it comes to clinical judgments. This leaves nurse
educators constantly looking for evidenced-based teaching/learning strategies to help
their students develop clinical reasoning. Parker, Giles, Lantry, and McMillan (2014)
posited the need to develop and test a range of evidenced-based strategies that will
empower nurses. In addition, these strategies can embed a systematic approach in nursing
graduates that will aid in their transition to practice. According to Parker et al., (2014)
new graduates are stressed by the expectations that they perform like a nurse with twenty
years of experience. Narrowing the education-practice gap will ease some of this stress
on new nursing graduates.
Determining the most effective strategies to develop clinical reasoning in nursing
education is key to successful transition into clinical practice and desired patient
outcomes (Kavanagh & Szweda, 2017). While researching teaching/learning strategies
that were most effective in facilitating clinical reasoning, I found the following
teaching/learning strategies that are effective in the development of clinical reasoning:
case studies and clinical scenarios, web-based case studies, case study or clinical scenario
with structured model or theory, clinical coaching, collaborative learning, concept
mapping, experiential or clinical practicum, reflective journaling, and simulation. Even
with this array of educational strategies available, new graduate nurses are still not

35
practice ready. More research is needed to develop and test additional educational
strategies that can enhance clinical reasoning.
McMillian & Dwyer (1989) posited that problem-based learning (PBL) has been
implemented as a learning strategy to promote clinical reasoning in many healthcare
fields. Problem-based learning is a strategy developed in the late 1960s at the McMaster
University Medical School in Hamilton, Ontario, Canada (Jones, 2008). This learning
strategy utilizes active and self-directed learning to promote analytical reasoning,
communication, and team problem-solving skills (Jones, 2008). Problems are the
framework for discussions not lectures. Breytenbach, Ham-Baloyi, and Jordan (2017)
identified PBL as a strategy that enhanced problem solving skills for real life problems.
Few studies have investigated the effects of different problem-based learning strategies
on clinical reasoning (Harmon & Thompson, 2015; Jessee & Tanner, 2016; Prosser &
Sze, 2014). Merisier, Larue, and Boyer (2018) posited that most of the studies concerning
PBL strategies involve their influence on critical thinking in nursing. Carvalho, et al.
(2017) identified PBL as the most commonly utilized teaching intervention for critical
thinking. With the focus in nursing shifting from critical thinking to clinical reasoning,
studies need to change their focus to clinical reasoning.
Wosinski, Belcher, Dürrenberger, Allin, Stormacq, and Gerson (2018) posited
that the goal of PBL is to improve clinical reasoning skills. Wosinski et al. (2018) noted a
lack of studies concerning individual learning strategies to help nursing students master
PBL, leaving an opening for future research. This study used a meta-synthesis approach.
Questioning is one of the most frequently used PBL strategies in raising a student’s

36
cognitive ability (Gilkison, 2003). Merisier, Larue, and Boyer (2018) reasoned that
questioning, as a PBL teaching strategy, would influence clinical decision making. While
it appears that the use of questioning influences clinical reasoning, there is no empirical
evidence to support the assumption (Merisier et al., 2018). Providing nurse educators
with evidenced-based teaching/learning strategies effective in the development of clinical
reasoning and judgment, will help future nurses provide safe, quality care. I propose to
study the influence of questioning on the development of clinical reasoning using
Lasater’s clinical judgment rubric as an instrument of measurement (Lasater, 2011).
Wuryanto, Rahayu, Emilia, Harsono, and Octavia (2017) presented a study on an
outcome present test-peer learning (OPT-peer learning) model to develop clinical
reasoning in nursing students who specialize in ICU. This study was qualitative in nature
and emphasized a phenomenology approach. This learning strategy is based on Bandura’s
learning theory of self-efficacy. Bandura’s learning theory envisions that one’s ability to
solve problems increases when they see interventions bring about desired outcomes
(Wuryanto et al., 2017). The learning strategy used is a peer learning strategy that uses
group problem solving and reflection. The strategy incorporates a reversal way of
thinking to change the client from the current state to the desired state.
Strengths and Weaknesses of Past Research Approaches
The greatest strength of the Breytenbach et al. (2017) integrative review was the
inclusiveness of teaching strategies available for nurse educators. Breytenbach et al.,
(2017) supported that nurse educators should use a variety of teaching strategies and that
37
educators be properly trained in their use. It was suggested that additional research be
done on identifying which combinations of strategies would be beneficial.
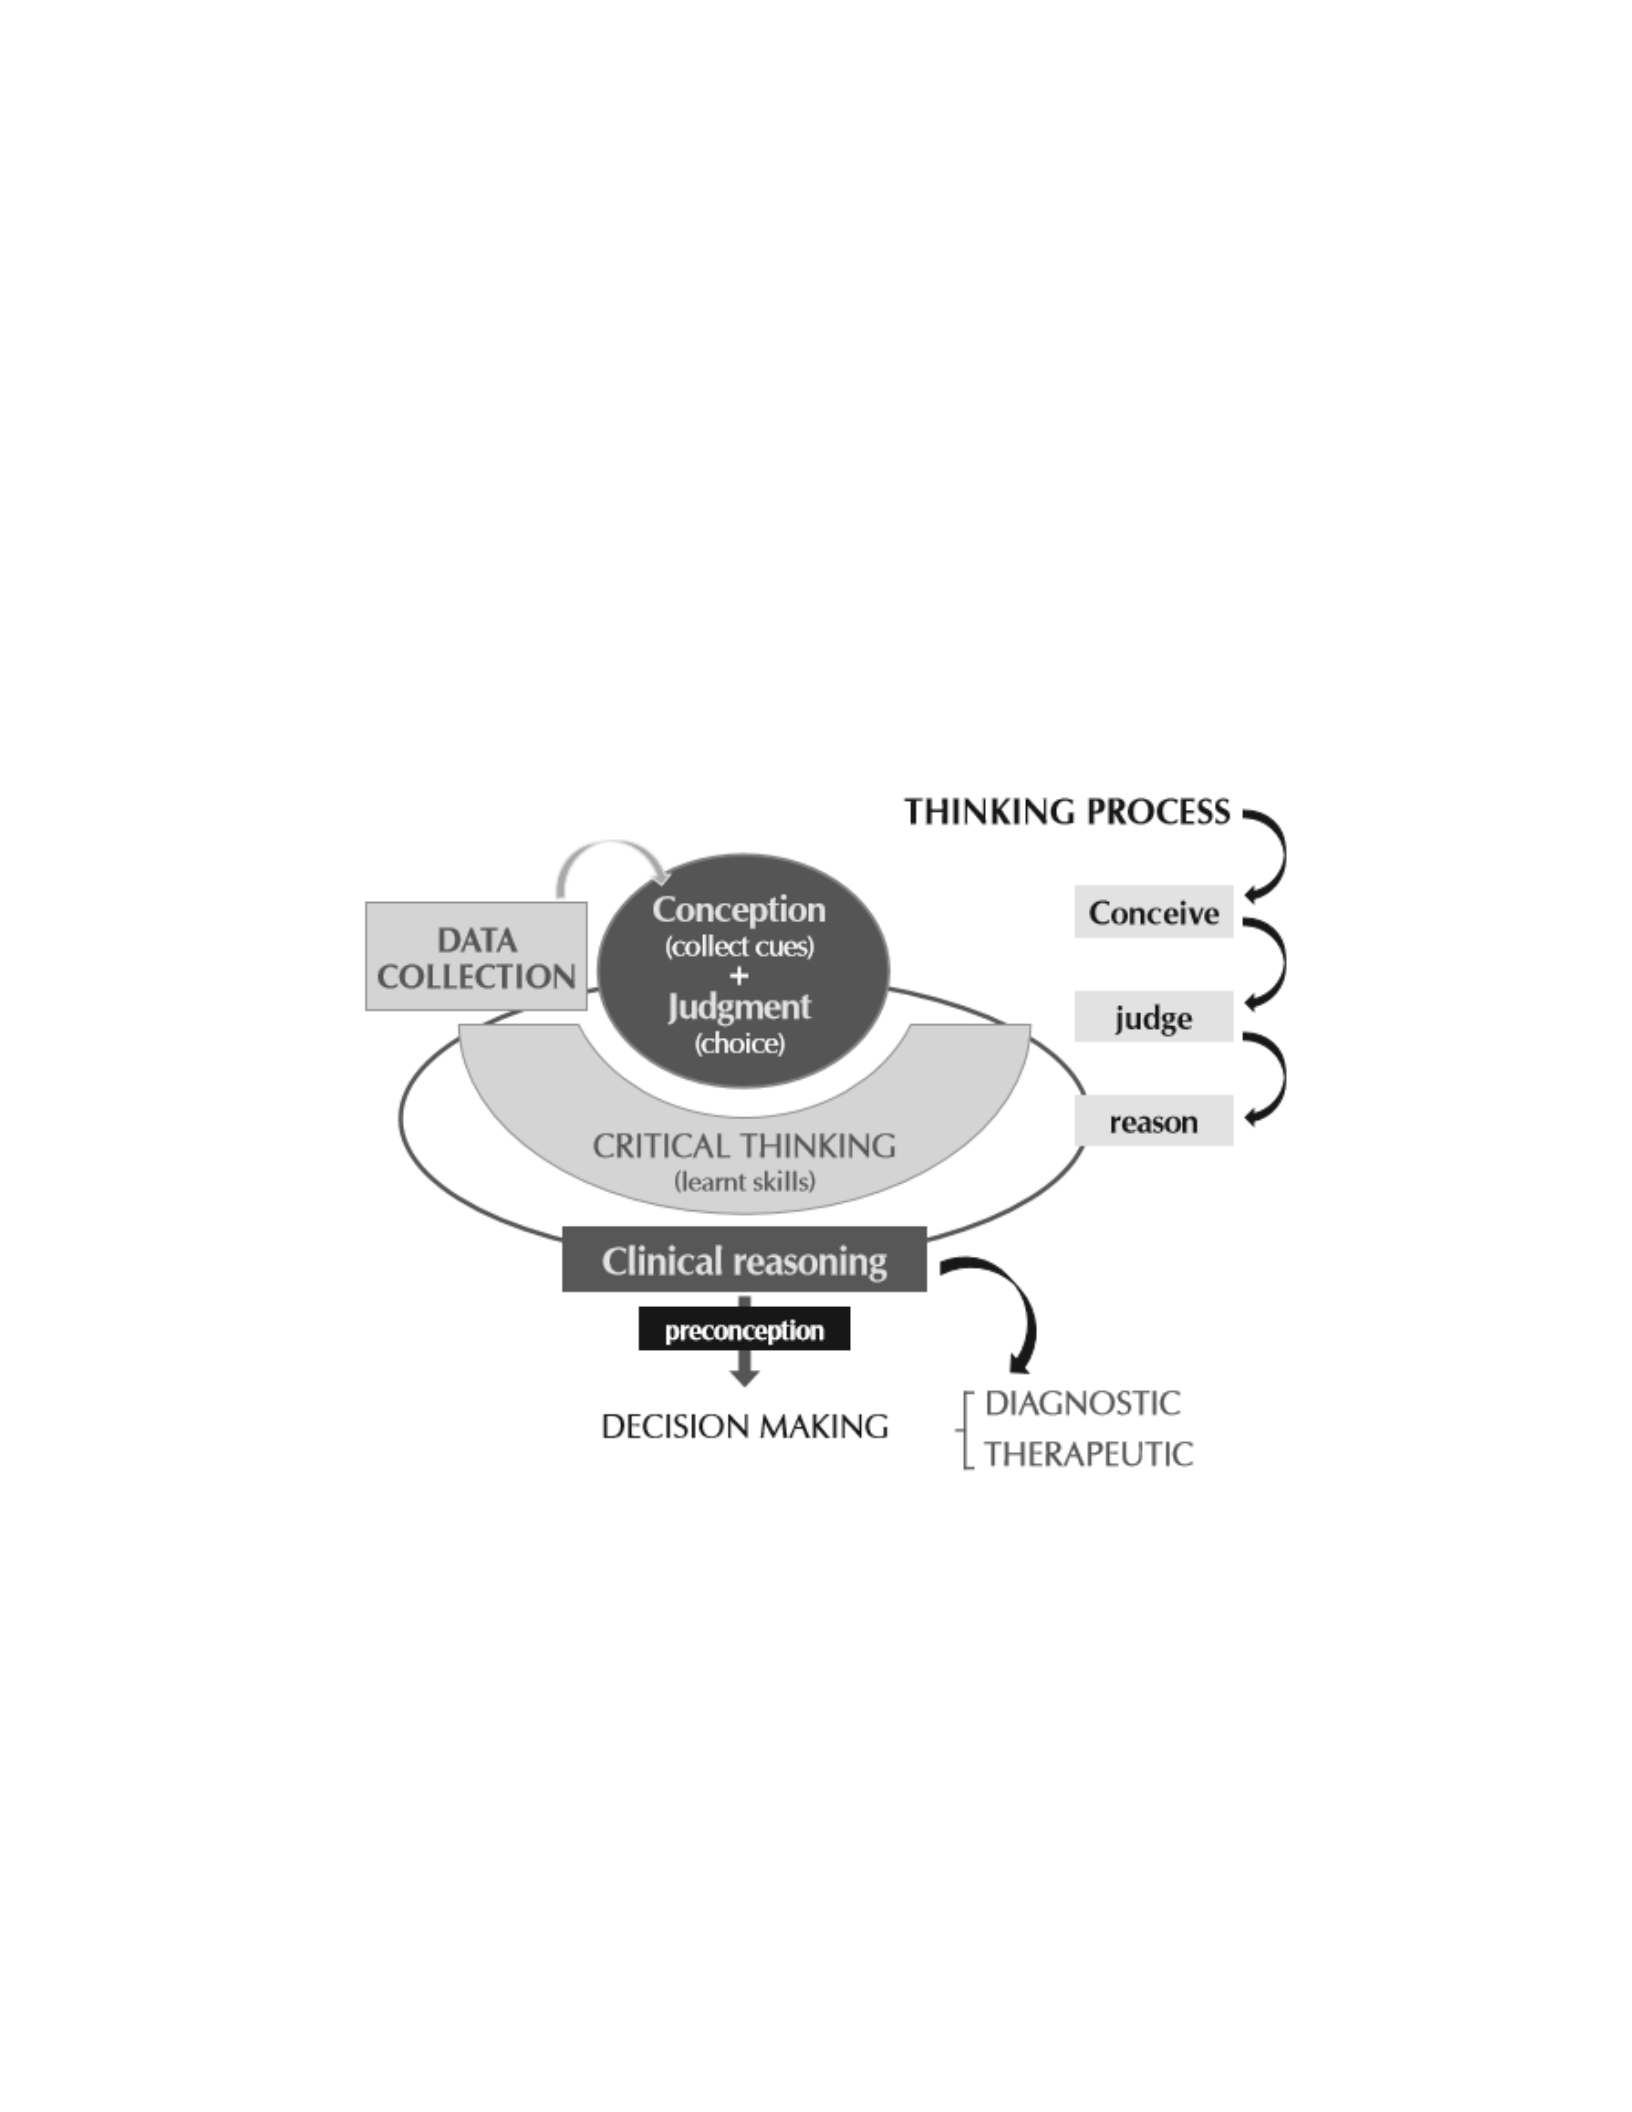
The greatest strength of the Carvalho et al. (2017) study was the descriptions of the
critical thinking and clinical reasoning strategies identified. Also. the steps in the clinical
reasoning process are well defined See Figure 2.
Figure 2
Thinking Process
The Wosinski et al. (2018) study was unable to fully support the objectives of
identifying and synthesizing the perspectives of undergraduate nursing students
concerning strategies to assist with their success in PBL due to the lack of evidence on
specific learning strategies. Another study, the Wuryanto et al., study identified some
critical limitations. First, the clinical faculty did not provide optimal guidance. In

38
addition, the student-patient ratio was not consistent. The strength of the study was that
they identified that PBL aided nursing students in the acquisition of skills that foster
clinical reasoning. Strengths of the Wuryanto et al. (2017) study were also identified. The
OPT-peer learning model was effective as a clinical reasoning learning strategy.
Benner, Sutphen, Leonard, and Day (2010) called for a radical transformation in the
education of nurses. They believed that nursing education should bring effective teaching
strategies such as experiential learning and coaching into the classroom. Benner et al.
(2010, p. 82-86) identified four essential shifts for integration:
• Shift from a focus on covering decontextualized knowledge to an emphasis on
teaching for a sense of salience, situational cognition, and action in particular
situations,
• Shift from a sharp separation of clinical and classroom teaching to integration of
classroom and clinical teaching,
• Shift from an emphasis on critical thinking to an emphasis on clinical reasoning
and multiple ways of thinking that include critical thinking, and
• Shift from an emphasis on socialization and role taking to an emphasis on
formation.
Learning to think like a nurse involves more than just focusing on contextual
knowledge. Nursing students need to grasp an understanding of the situation, what is
important and what is not. To achieve this, nursing students must learn to quickly assess
and identify relative cues to the situation (Benner, et al., 2010). For example, a patient
may exhibit a decrease in urine output and an increase in heart rate. Together, these cues

39
should trigger a nurse to explore for other manifestation of shock. The integration of
clinical situations into the classroom is imperative for nursing students to build a sense of
confidence as conditions change in the clinical settings.
The need to shift from critical thinking to clinical reasoning becomes more evident as
patients present with increasingly complex situations. Benner et al. (2010) posited that
critical thinking has become such a catch-all phrase in nursing in the pursuit of sound
clinical judgments. While critical thinking is an important component to assist the nurse
in clinical judgments, it is not all that is needed to make sound clinical judgments.
Nursing students use a variety of forms of thinking; critical, creative, scientific, and
formal empirical thinking to make clinical judgments. The also use clinical reasoning and
clinical imagination to make decisions. This shift in nursing education allows graduate
nurses to take into account the what-if questions by using creative, critical, scientific, and
critical thinking to make sound clinical decisions. Benner et al. (2010) described clinical
reasoning as the ability to reason with changes in clinical situations, all while taking into
account the context and any concerns from the patient and/or family. Benner et al. (2010)
believed that formation is critical in role development. Formation is the method by which
someone is “made capable of functioning in a particular role” (Benner et al., 2010). My
interest is the development of clinical reasoning in nursing students.
Rationale for Selection of Variables
Sedgwick, Grigg, and Dersch (2014) posited that the problem with nursing
education is a matter of instilling the basic elements of reasoning into the daily activities
of instruction leaving new graduates less than practice ready. Wolff, Pesut, and Regan

40
(2010) defined practice ready as “new graduates who are able to make the transition from
student to professional nurse.” Current acute healthcare environments are complex
requiring nurses to possess sound clinical reasoning skills that allows them to recognize
salient cues that suggest a decline in patient condition (Jessee, 2018). Patients’ outcomes
depend on nurses’ abilities to reason clinically to make sound clinical judgments
(Dickson et al, 2018; Jessee, 2018; Tyo & McCurry, 2019). A gap in the literature exists
identifying current educational strategies that are effective in clinical reasoning (Merisier
et al., 2018; Tyo & McCurry, 2019). Levett-Jones et al. (2010) posited that current
teaching and learning strategies may fall short in the development of clinical reasoning
skills.
Problem-based teaching/learning strategies have been shown to promote clinical
reasoning in healthcare (Barrows and Tamblyn, 1980; Barrows, 1986: Merisier et al.,
2018). This teaching/learning strategy utilizes active and self-directed learning to
promote analytical reasoning, communication, and team problem-solving skills (Jones,
2008). In PBL, the clinical problems solved by the students are the basis for learning
rather than lectures presented by the instructors. Breytenbach, Ham-Baloyi, and Jordan
(2017) identified PBL as a strategy that enhanced problem solving skills for real life
problems. Few studies have investigated the effects of different problem-based
teaching/learning strategies on clinical reasoning (Breytenbach, Ham-Baloyi, & Jordan,
2017). Merisier, Larue, and Boyer (2018) posited that most of the studies concerning
PBL strategies involve their influence on critical thinking in nursing. Carvalho, et al.
(2017) posited that PBL is the most commonly used teaching intervention in the

41
development of critical thinking. Rakhudu, Davhana-Maselesele, and Useh (2016)
describe PBL as one of the most innovative educational strategies used in health sciences
education. Prosser and Sze (2014) concluded that programs that used PBL outperformed
traditional programs in the application of skills and clinical reasoning.
In an early study Larue (2008) posited that the development of clinical reasoning
was dependent on the educational strategies used in its development. Larue (2008)
observed that nursing students used memorization strategies similar to Barrows’ findings
of medical students (Barrows, 1986). Memorization of facts provided superficial
understanding and was not transferable as patient conditions changed. Barrows brought
problem-based learning into healthcare education to deepen understanding and to develop
clinical reasoning in medical students. Tamblyn was responsible to transitioning
problem-based learning to nursing education (Barrows & Tamblyn, 1980).
Questioning is one of the most frequently used problem-based learning strategies
(Merisier et al., 2018). Questioning as a teaching/learning strategy has been linked to
critical thinking. However, Merisier et al. (2018) could find little empirical evidence
linking questioning to clinical reasoning. I also was unable to find any studies that linked
questioning as an effective strategy in the development of clinical reasoning. Questioning
has been linked to critical thinking but not to clinical reasoning (Browne & Keeley, 1990;
Merisier et al., 2018; Sellappah, Hussey, Blackmore, & McMurray, 1998).
Clinical Reasoning/Clinical Judgment
Clinical reasoning is the basis of every decision in nursing (Merisier, Larue, and
Boyer, 2018). Tyo and McCurry (2019) explained that the literature does not agree on

42
just one definition of clinical reasoning. The fact that clinical reasoning is a complex
decision-making process that involves knowledge specific to the discipline, several
methods of thinking, and reasoning skills is agreed upon by most (Tyo & McCurry,
2019). Vallente (2016) describes clinical reasoning as a thought process used by
healthcare professionals where they gather and analyze patient information or cues,
determine the relevance of the information, and look for potential interventions that could
improve the patient outcomes. Levett-Jones, Hoffman, Dempsey, Jeong, Noble, Norton,
Roche, and Hickey (2010) define clinical reasoning as “the process by which nurses
collect cues, process information, come to an understanding of a patient problem or
situation, plan and implement interventions, evaluate outcomes, and reflect on a learn
from the process.” A cue is a piece of patient data that is either objective or subjective
that requires a healthcare professional to make inferences to the situation or problem.
Nurses who do not possess clinical reasoning skills are likely to make poor
clinical judgments while nurses with good clinical reasoning skills are likely to have a
positive impact on patient outcomes (Tyo & McCurry, 2019). Sedgwick and Dersch
(2014) found that novice nurses are more likely to make decisions using a linear process.
With this process, tacit dimensions of the problems are not considered. This presents with
a much slower reasoning process as nurses work through complex patient problems.
Failure to recognize cues or changes in condition in a timely manner can lead to a
worsening condition.
Clinical reasoning skills are built over time with experience and knowledge
integrated with self-awareness, social, psychosocial, cultural, and contextual influences

43
(Sedgwick & Dersch, 2014). Development of clinical reasoning cannot wait until after
graduation. A strong focus on clinical reasoning in nursing education is essential in the
preparation of new graduates as they enter clinical practice (Institute of Medicine, 2010;
Kavanagh & Szweda, 2017).
Consideration of several factors including self, patient and situation are required
for skilled clinical reasoning. Nurses who possess self-awareness are more likely to see
the need to think more broadly and deeply. They are able to prioritize interventions and
ask relevant questions within the current context. They are also more likely to revisit
answers to those questions to increase their experiential knowledge (Herron, 2017). This
allows for better decision making when evidence is present (Sedgwick & Dersch, 2014).
Understanding the full context of the patient’s situation is crucial. Taking into
consideration a patient’s overall health, resilience, and support can impact clinical
decisional making. The situation can include the timing or acuteness of the problem along
with the environment in which the situation occurs
Many nurse educators teach how they were taught using a curriculum saturated
with content (Kavanagh & Szweda, 2017). Most nurse educators also evaluate student
nurses’ thinking processes based-on the nursing process (Gonzalez, 2018). Clinical
reasoning and the nursing process are not equal. The nursing process is liner in thought
and fails to capture more complex clinical reasoning concepts (Gonzalez, 2018). The
nursing process, while linear, does require critical thinking in the planning of care.
Nursing process does not allow for more complex thought process needed for clinical
reasoning such as analysis, intuition, and narrative thinking (Tanner, 2006). Gonzalez

44
(2018) described the framework of Tanner’s Clinical Judgment Model and the Lasater
Clinical Judgment Rubric as ideal for teaching clinical reasoning due to the insight into
how nurses think when making clinical judgments and the development of that thinking.
Gonzalez (2018) used a concept-based approach to develop clinical reasoning in
the clinical setting. Each week a different theme was presented, along with clinical
lessons, learning opportunities, and activities. The clinical lessons demonstrated how
nurses use clinical reasoning throughout their shift. The lessons showcased the cognitive
process used by nurses and then allowed opportunities for students to practice in the
healthcare setting. Concept-based teaching helps to show common threads that students
can piece together, breaking clinical reasoning into smaller, more manageable pieces of
information (Gonzalez, 2018).
Assessing clinical judgment and clinical reasoning is a priority among nurse
educators (Dickson, Haerling, & Lasater, 2018). The National Council of State Boards of
Nursing Clinical Judgment Model (NCSBN-CJM) was developed to assist in the
development of tools for assessing clinical judgment by nurse educators (Dickson et al.,
2018). The NCSBN-CJM is a multi-layered model that include observation, cognitive
operations, and contextual factors (Dickson et al., 2018). By defining the specific layer of
the model, nurse educators can evaluate student clinical judgment abilities with
observable identified actions.
Harmon and Thompson (2015) studied the use of collaborative activities as a
teaching strategy for improving clinical reasoning in nursing students. Harmon and
Thompson (2015) used a quasi-experimental one-group time-series design for their study.

45
The OPT model was used as the data collection tool. It was noted that while collaboration
improved scores in clinical reasoning, the overall scores were low, indicating low clinical
reasoning skills (Harmon & Thompson, 2015). Some cited possible reasons for the
overall low scores were incomplete data due to some students missing time, incomplete
worksheets due to misunderstanding on proper procedure for completing the OPT
worksheet, and students’ inexperience with group learning. Limitation of the study were
the small sample group and a time frame of eight weeks may not be adequate to
demonstrate improvement in clinical reasoning.
Clinical reasoning develops over time. A novice thinker does best with well-
defined tasks where analysis is usually a rule-based process (Jessee, 2018). The novice
thinker has difficulty identifying subtle changes in patient conditions when they fall out
of an expected frame of reference. Over time the nurse becomes an expert reasoner,
shifting patterns of thinking. This shift may be anywhere along the continuum between
intuition to analytic, taking into account depth of knowledge and experience.
Problem-Based Learning
PBL is an active teaching strategy that is student-centered where students use
their knowledge and skills to solve ill-structured problems (Barrows, 2000). Barrows and
Tamblyn (1980) posited that students learn through solving problems and using
reflections of past experiences. Barrows (1986) believed that instructors should guide
students in their learning but that students should take responsibility for their own
learning. Barrows first used PBL at McMaster University as a way to improve clinical
reasoning in medical students. His premise was that physicians had difficulty transferring

46
knowledge learned in medical school to the variety of problems they saw in practice.
Through PBL, medical students were able to take current knowledge and past
experiences to solve problems that could not be solve with a simple algorithm (Barrows,
2000). Students were required to look at alternatives and support the reasoning for their
selections. He noted key objectives and characteristics of PBL that were different than
traditional teaching methods (see Figure 3). Seeing the usefulness of this approach
Tamblyn, a professor in nursing, introduced problem-based learning to other healthcare
disciplines, including nursing (Barrows & Tamblyn, 1980).
Figure 3
Objectives and Key Characteristics of PBL
Objectives
Key Characteristics
• Structuring knowledge for use in
clinical contexts
• Developing an effective clinical
reasoning
• Developing effective self-directed
learning skills
• Increasing motivation for learning
• Learning is student-centered
• Learning occurs in small groups
• Teachers are facilitators or guides
• Problems used as the organizing focus
and stimulus for learning
• Problems are a vehicle for the
development of clinical problem-
solving skills
• New information is acquired through
self-directed learning
Note. Key objectives and characteristics of problem-based learning. Adopted from “A
problem-based learning in medicine and beyond: A brief overview” by H. S. Barrows,
(1996, 5-6), New Directions for Teaching and Learning.
Much like the medical students in Barrow’s study, PBL can help nursing students
use their knowledge and problem-solving skills to overcome barriers in clinical practice.
Nurses are continuously challenged with complex patient problems. Like Barrows’ ill-

47
structured problems, these problems or changes in conditions are not always solvable
with a simple algorithm. They require the nurse to tap into their knowledge and previous
experiences to present possible solutions or alternatives to the problem. By the late
1990s, many nursing programs had added PBL teaching methodologies to their curricula
to help develop clinical reasoning, self-evaluation, collaboration, and communication
skills (Shin and Kim, 2013). In a meta-analysis of 22 articles on PBL in nursing students,
Shin and Kim (2013) found that PBL in nursing education showed that PBL had a
positive effect on clinical education of nurses in the development of their clinical
reasoning skills. Other studies have shown a positive effect of PBL in nursing education
(Jones, 2008; Prosser & Sze, 2014; Sanestani & Khatiban, 2013). Prosser and Sze (2014)
found PBL courses to be beneficial due to the long-term retention of course content.
These courses also allowed for short-term retention that involved elaboration of
information, new skills, and clinical reasoning.
PBL uses a deep approach to learning by focusing on longer-term retention,
understanding, and even the application of new knowledge. This is in contrast to a
surface approach to learning where students’ learning focuses on the short-term outcome
such as studying for an exam. Prosser and Sze (2014) posited that if the focus of learning
was to pass and examination, then the surface method of learning was appropriate.
However, if the focus of learning was for long-term retention and application in a clinical
setting, the deep approach to learning was preferred by students and educators.
Students have more control over their learning with PBL than with the traditional
teacher centered approach. Students can determine what they need to learn as many bring

48
knowledge from varied experiences. PBL is usually carried out in small group
discussions using collaboration with each other to explore alternatives in problem solving
(Rakhudu, Davhana-Maselesele, & Useh, 2016). Educational institutions can also
collaborate with clinical partners in the education and development of clinical reasoning
in students. The common goal of this collaboration is the development of practice ready
nurses upon graduation of the nursing program.
Questioning/Inquiry
Merisier, Larue, and Boyer (2018) noted questioning to be one of the oldest used
strategies in the development of student reasoning dating back to the early Greek
philosopher Socrates. Questioning has been studied for it effect on critical thinking but
not on its effect of clinical reasoning. Critical thinking is a general thinking process while
clinical reasoning is a process that incorporates all types of thinking to include critical
thinking (Benner et al. 2010). Clinical reasoning is a thinking process that takes into
account the clinical context while analyzing data. Clinical thinking is required by clinical
reasoning, leading one to believe that questioning as an educational strategy should also
affect clinical reasoning.
The concept of questioning is embedded in the clinical judgment model. In
particular, questioning fits the model’s first step of noticing. Debriefing post simulation is
an evidenced-based strategy to increase clinical reasoning in nursing students (Ashley &
Stamp, 2014). During debriefing, students typically describe their thoughts and feelings
on a situation that just occurred. Learning to think like a nurse requires a variety of
reasoning patterns, when working through a patient problem or situation, that may be a

49
combination of intuitive, analytical, and narrative input. For assessments to be effective,
students must notice the cues presented by their patients. This noticing is the first step in
Tanner’s (2006) clinical judgment model. With debriefing, instructors can provide
questions based on student performance to guide them into thinking like a nurse.
Reflection is another teaching/learning strategy used in the development of
clinical reasoning and is the last step in Tanner’s (2006) clinical judgment model.
Students may reflect-in-action or reflect-on-action (Koharchik, Caputi, Robb, &
Culleiton, 2016; Tanner, 2006). Reflection-in-action is the nurse’s ability to interpret the
patient’s response to the intervention. Reflection-on-action as the subsequent thinking the
nurse has about the situation and what they have learned from it. Reflection-in-action is
one way an instructor can provide the student time to think about the activity and
determine what they learned, correct their thinking if needed, and use what they learn in
future situations (Koharchik, Caputi, Robb, & Culleiton, 2016). Reflection-on-action is
typically a writing activity that where the student dissects the whole patient encounter
with the intent of increasing knowledge and judgment (Koharchik, Caputi, Robb, &
Culleiton, 2016).
While questioning is used in both debriefing and reflection, there are no studies
on questioning as a teaching/learning strategy specifically in the development of clinical
reasoning. Most studies that assess questioning are related to critical thinking (Gilkison,
2003; Gul et al., 2014; Phillips et al, 2017). Gilkison’s (2003) study was the most closely
related study to my proposed research. Gilkison used questions by tutors to elevate the
cognitive level of discussions within the tutoring groups. These studies found that clinical

50
educators were more likely to use lower cognitive level questions than higher cognitive
questions.
Summary and Conclusions
The major themes of this study are clinical reasoning, PBL and questioning.
Clinical reasoning is the process nurses use to make clinical judgments. This process
includes a variety of ways of thinking. Tanner (2006) described these processes in the
first three steps of her clinical judgment model as noticing, interpreting, responding, and
reflecting. PBL is a strategy that is student-centered requiring students use their
knowledge and skills to solve ill-structured problems (Barrows, 2000). Questioning is a
teaching/learning strategy designed to stimulate a deeper, higher level of cognitive
learning.
Patients’ outcomes depend on nurses’ abilities to reason clinically and to make
sound clinical judgments (Dickson et al., 2018; Jessee, 2018; Tyo & McCurry, 2019).
Teaching nursing student to reason clinically will allow them to make better clinical
judgments, closing the gap from academia to practice. Looking at teaching/learning
strategies that help develop clinical reasoning, I found the following: case studies and
clinical scenarios, web-based case studies, case study with a structured model or theory,
clinical coaching, collaborative learning, concept mapping, experiential or clinical
practicum, reflective journaling, and simulation (Tyo & McCurry, 2019). I was unable to
find any published studies that used questioning as a teaching/learning strategy in the
development of clinical reasoning in nursing students.

51
PBL has been shown to improve clinical reasoning in other healthcare field such
as medicine. Questioning was listed as one of the most frequently used PBL learning
strategies. Thus, questioning should affect clinical reasoning in nursing students.
However, I found few studies that directly link questioning to clinical reasoning. Clinical
education uses questioning as a teaching/learning strategy but I found limited studies on
the effect of questioning or inquiry on clinical reasoning. As an educator, I sought
evidence on which to base my teaching/learning strategies. The few articles identified
looked at either the level of questions being asked or related questioning to critical
thinking rather than the efficacy of questioning on clinical reasoning.
Benner (2015) proposed that nursing education shift their way of thinking about
pedagogies based on the Carnegie National Nursing Education Study in the United
States. I will use the five shifts identified by Benner to guide my assessment of
questioning in the development of clinical reasoning in nursing students. First, nursing
education needs to shift from surface or superficial learning to deep learning. Second,
academia needs to not only focus on the acquisition of knowledge, but also on how to use
that knowledge in actual practice. Third, the emphasis must move from a focus on critical
thinking to clinical reasoning with multiple ways of thinking. Fourth, teaching/learning
must be student-centered with the student playing an active role in formation. The fifth
and final shift is departing from teaching abstract formal theories and expecting students
to apply them to a focus on inductive, conceptualized use of knowledge by having
students analyze, synthesize, and evaluate information. These shifts are evident in the
Lasater’s clinical judgment rubric.

52
To help fill this gap of identifying educational strategies that are effective in the
development of clinical reasoning skills, this study will utilize retrospective data obtained
from a structured simulation with guided questioning that incorporated the shifts
proposed by Benner for nursing education. To ensure that questioning as a
teaching/learning strategy is the only potential reason for a change in clinical reasoning,
retrospective data will be obtained from the pre-evaluation, introduction of questioning as
a teaching/learning strategy, and data from a post evaluation. The results of this study
will provide evidence as to the influence of questioning on clinical reasoning in
prelicensure nursing students, extending the knowledge of nursing education
teaching/learning strategies. In Chapter 3, I will outline the research methodology that
guides this study.

53
Chapter 3: Research Method
Using the framework of Tanner’s clinical judgment model, the purpose of this
study was to explore the influence of questioning, a problem-based teaching/learning
strategy, on the development of clinical reasoning in undergraduate nursing students.
PBL is one of the most used learning strategies to foster clinical reasoning (Merisier et
al., 2018). Larue (2008) posited that while PBL creates a learning environment for
fostering the development of clinical reasoning skills, educational strategies used will
determine the success of the outcomes. There was little in the literature on the
effectiveness of different problem-based educational strategies in the development of
clinical reasoning. This study was in response to the challenge made by Harmon and
Thompson (2015) to nurse educators to develop and test teaching/learning strategies to
foster the development of clinical reasoning in nursing students. The PBL strategy of
questioning was selected to test its influence on clinical reasoning in nursing students
since it is one of the more prominent PBL strategies.
In this chapter, I explain the methodology used in this study. The research design
and rationale section covers the study variables, the research design selection and
rationale, the research question, and the intervention. The methodology section covers all
procedures used for the study that would enable another researcher to replicate the study.
Components are the population, sample and sampling procedures, procedures for
recruitment and data collection, and clear instructions for the use of the intervention of
questioning. This chapter also describes the instrument used for the collection of the data,
any threat to validity, and ethical procedures.

54
Quantitative Research Design and Rationale
The research question for this study was:
RQ-Quantitative: To what extent does the use of questioning, as a problem-based
teaching/learning strategy, influence the development of clinical reasoning in
undergraduate nursing students?
H0: Questioning as a problem-based learning strategy has no influence on the
development of clinical reasoning in undergraduate nursing students.
Ha: Questioning as a problem-based learning strategy influences the development
of clinical reasoning in undergraduate nursing students.
A quantitative research design was selected as a means of testing the relationships
among the variables (Creswell, 2014). The study investigated the relationship between
the independent variable of “questioning” and the dependent variable of “clinical
reasoning”. A quasi-experimental one group ex post facto design was conducted using
secondary data. The specific type of quantitative research method was analytical in nature
using a pretest/posttest design (Forister & Blessing, 2016). I evaluated if the independent
variable (questioning) influenced the dependent variable (clinical reasoning) and the
extent to which the dependent variable was affected by the independent variable. The
study used data from a simulation experience required by the college as part of the
students’ routine clinical experiences. Students participated in a simulation experience
and were asked to complete a clinical judgment tool based on their experience. The
students were then asked a series of open-ended questions to elicit a deeper thought
process prior to repeating the simulation. After completion of the second simulation, the

55
students completed the clinical judgment tool a second time. The clinical judgment tool
used for clinical evaluation was developed by the college based on the LCJR. The design
choice of one group ex post facto was chosen as it matched the secondary data available
to test the educational strategy of questioning.
The intervention for the study was a set of guided open-ended questions used to
deepen the students thought processes (see Appendix 3). The set of guided questions was
the independent variable for the study. The data was collected retrospectively,
eliminating a potential time constraint that might exist due to the program’s structuring of
courses. There were no financial constraints identified except for the researcher’s time.
Research is needed to advance knowledge in all disciplines including nursing.
Cipriano (2007) described five ways of knowing to assist in understanding how
knowledge is obtained: empirical knowing, ethical knowing, personal knowing, aesthetic
knowing and synthesis of the other four types of knowing. Empirical knowing is based on
facts obtained from quantitative research. The focus of ethical knowing is a person’s
moral values. Personal knowing focuses on relationships between people and knowing
oneself. Perception with an emphasis on the uniqueness of relationships and interaction is
the focus of aesthetic knowing. While all forms of knowing are importing when
providing patient care, empirical knowledge is of utmost importance to the advancement
of knowledge in the discipline. This study provided empirical evidence to the influence of
questioning as an educational strategy on the development of clinical reasoning,
strengthening the knowledge of the discipline.

56
Methodology
Descriptions of the population of interest, the type of sampling, sampling
procedures, and procedures for recruitment are discussed in this methodology section. In
addition, this section will explain the type of data collection, procedures for data analysis,
the tool used to measure clinical reasoning and judgment in nursing students pre and
postintervention of the teaching/learning strategy of questioning.
Population
The target population for this study was deidentified secondary data obtained
from prelicensure nursing students school records. I assigned the same number to the
pretest and posttest of each student to ensure comparison accuracy of the data collection
process. Data was obtained from records of students who were enrolled in their last
lower-level clinical course. The secondary data was obtained from a population of
nursing students who were enrolled in a small community college in the southeastern
United States between 2017 - 2019. The research examined the retrospective data from
three cohorts in the same clinical course providing an oversampling size of approximately
100 students to ensure an adequate number of students have completed all the data on the
tool. 42 students will be randomly selected from this sample to meet the sample size of
34 indicated by the power analysis. This was approximately a 20% increase in sample
size, in the event of I ran across any tools with incomplete data. Only completed tools
with a preintervention and postintervention evaluation were used.

57
Sampling and Sampling Procedures
Retrospective data obtained from records of nursing students enrolled in their last
lower-level clinical course was used for the study. The records used in this retrospective
study were taken from records of students who were required to participate in simulation
experiences as a portion of their clinical experiences for this clinical course. Because
retrospective deidentified data was used, student permission was not needed. However,
permission for the use of the data was granted by the Director of Health Sciences and the
Dean of Instruction from the community college. Inclusion criteria for participation in the
current study were the records of nursing students in their first upper-level clinical course
who completed both a pre-intervention and postintervention clinical judgment tool.
Exclusion criteria for participation in the study included nursing students who failed to
complete both a preintervention and a postintervention clinical judgment tool.
Power Analysis for effect size, alpha level, and power level
The online power analysis tool G* Power 3 (Faul et al., 2007) was used to
calculate sample size for a test of means using two dependent groups of matched pairs.
This type of paired sample is sometimes referred to a repeated measures design since the
research design repeats the assessment on the same group (Grove, Burns, & Gray, 2013).
Qualifiers of effect size of .50, a power = .80, and an alpha = .05 were used to calculate
the sample size based on standard acceptable research values (Creswell, 2014; Monagle
et al., 2018). The online power analysis tool G* Power 3 (Faul, Erdfelder, Lang, &
Buchner, 2007) indicated that a sample size of 34 would allow for a positive medium
sized effect between the pre and postintervention groups while assuming a power = .80,

58
and an alpha = .05. A sample pool of approximately 100 was used to ensure that an ample
sample size of completed data is obtained.
Procedures for Recruitment, Participation, and Data Collection
A request to use 2017 - 2019 retrospective data from a simulation experience
incorporated into the curriculum was approved by the Director of Health Sciences and the
Dean of Instruction. For recruitment for the study to be a possibility, approval from the
Institutional Review Board (IRB) was obtained from Walden University and the
community college. Demographic data obtained included age and gender. The evaluation
tool contained no identifiers beyond a number and the demographic information needed
for the study. No informed consent was required due to the use of retrospective data.
The data collected was from a single simulation in the clinical course repeated
throughout the semester for three consecutive years. The students were scheduled for an
eight-hour simulation experience as part of their required clinical experience. All students
arrived at the simulation where a pre-briefing of the scenario occurred that included the
objectives of the simulation. The students participated in the simulation activity and were
requested to complete the clinical judgment tool (Appendix A) based on Tanner’s clinical
judgment model and Lasater’s clinical judgment rubric (Appendix B). Next, the students
were asked a series of guided questions to encourage discussion and deeper thinking
(Appendix C). The students repeated the simulation and were then asked to redo the
clinical judgment tool. All information entered by the students used in the analysis was
scored using the Lasater clinical judgment rubric.

59
The simulation consisted of four nursing students per simulation group. After the
simulation, the students completed the clinical judgment tool. The instructor then asked a
series of guided, open-ended questions to stimulate deeper thought process prior to
repeating the simulation. The students then completed the clinical judgment tool for a
second time. The simulation was repeated over the course of the semester until all
students in the course completed the simulation. Each student was required to sign a
confidentiality statement concerning simulation. Secondary data from the clinical
judgment tools was evaluated retrospectively using the Lasater clinical judgment rubric.
Lasater’s clinical judgment rubric has 11 components for measurement. Each component
will be scored based on the rubric’s levels using the following numerical values: one
point for beginning, two points for developing, three points for accomplished, and four
points for exemplary. Each student’s pre and postintervention tools were given a score
and compared to determine if the educational strategy of questioning influenced the
development of clinical reasoning. Intrarater repeatability will be performed to ensure
consistency in scoring (Ergai, et al., 2016; Kaur, et al., 2014).
Instrumentation and Operational Constructs
Lasater clinical judgment rubric
The instrument used to evaluate the secondary data was the LCJR developed and
published in 2007 (Lasater, 2007). The tool was designed to evaluate clinical judgment in
nursing students based on the framework of Tanner’s clinical judgment model (2006).
The rubric describes levels of performance in clinical judgment. The tool is appropriate
for the evaluation of clinical reasoning as clinical reasoning is the thought process that

60
nurses and other health care clinicians make their clinical judgments. The first three
components of Tanner’s clinical judgment model, noticing, interpreting, and responding,
are all part of the thought processed used to make clinical judgments. The last component
of reflecting aids in the evaluation of the thought processes used in the clinical judgment
and allows the nurse to gain a knowledge of what has occurred as a result of the nursing
actions. Tanner’s clinical judgment model demonstrates a variety of reasoning processes
from analytical to intuitive (Lasater, 2007).
Lasater’s clinical judgment rubric identifies two to four dimensions per
component of Tanner’s clinical judgment model for a total of 11 dimensions. There are
performance indicators for each dimension, identifying four levels of development
(beginning, 1 point; developing, 2 points; accomplished, 3 points, and exemplary, 4
points) for a possible score range of 11 to 44. The rubric helps identify gaps in student’s
understanding which may have gone unnoticed. This allows for instructors to offer timely
and meaningful feedback. The rubric was developed to describe the development of
clinical judgment and was pilot tested in a simulation laboratory.
The reliability and validity of the tool was established in the Adamson study in
2011, the Gubrud-Howe study in 2008, and the Sideras study in 2007. The population for
each study was undergraduate nursing students. The Sideras study compensated for the
fact that the indicators were highly intercorrelated. Thus, the level of agreement was
expanded to one point, meaning that rates that varied by one point or less were
considered equal. The reliability percent varied over time and between pairs. At round
four, the percent of agreement ranged from r = 0.75 to 1.0. At round eight, the percent of

61
agreement ranged from r = 0.91 to 1.0. At round 13, the percent of agreement ranged
from r = 0.85 to 0.57. The validity results from the Sideras study showed sizable
differences between the two groups but supported the ability of the raters to evaluate the
clinical judgments using the LCJR. The Sideras study used the tool to evaluate the
differences in clinical judgment between junior and senior nursing students using three
simulation case scenarios.
The Gubrud-Howe study (2008) used only two raters and each rater received
training prior to rating using the LCJR. The interrater reliability indicated a mean score of
92% agreement between the raters. A one-way ANOVA was conducted to assess for any
significant differences in the raters with the following results: F ratios for all indicators
<4.84 with p values all >0.05. The Gubrud-Howe study used the instrument to understand
clinical judgment as instructional strategies were being developed for high-fidelity
simulation.
In the Adamson study, the raters also received training and the rater selection was
based on strict criteria. The interrater reliability results demonstrated a 95% confidence
interval. This study also measured validity demonstrating that the scores were consistent
with the intended levels. The Adamson study was used for assessing the reliability of
simulation evaluation instruments. I was the only evaluator of the clinical judgment tools
negating the concern of interrater reliability. I tested the results of the data for internal
consistency reliability using Cronbach’s alpha and compare that to published reliability
data.

62
Clinical Judgment Tool
The clinical judgment tool was compiled by the community college using the 11
dimensions of the LCJR (Lasater, 2011). The clinical judgment tool was devised as a way
for the students to organize their thought processes as they made their clinical judgments
(Appendix A). It provided a way for the faculty to evaluate their reasoning and to correct
any errors in reasoning in both clinical and simulation settings. This evaluation has been
subjective by the clinical and simulation faculty. Although this tool has not been
evaluated against the Lasater clinical judgment rubric by the community college it was
developed to specifically correlate to the Lasater clinical judgment rubric. After the initial
completion of the clinical judgment tool
additional open-ended questions were asked by the simulation faculty to encourage a
deeper thought process (Appendix C). The students were then asked to redo their clinical
judgment tool to include the additional questions.
Data Analysis Plan
Descriptive statistics and paired samples t test were used to compare the mean
differences between the preintervention and the postintervention group using the
Statistical Package for Social Sciences (SPSS), version 24 (I.B.M., 2016). There was an
assumption that there will be a normal distribution of the differences in the data for the
paired t test (Pandis, 2015). I provided a histogram to check for normal distribution. The
confidence interval was run with the default of 95%. Data that can be obtained from
running this paired samples t test included general statistics of mean, sample size,
standard deviation, standard error, and correlation between the two variables. The paired

63
samples t test was used to determine if there is a statistically significant difference
between the two variables. I tested internal consistency reliability using Cronbach’s alpha
for the LCJR.
Threats to Validity
Valid findings are needed to allow for the acceptance or rejection of the null
hypothesis. Threats to validity could raise questions on the usefulness and
appropriateness of the data collected and the conclusion made by the researcher
(Creswell, 2014: Forister & Blessing, 2016; Nieswiadomy & Baily, 2018). This section
will discuss threats to external, internal, construct, and statistical conclusion validity. The
importance of mitigating threats to validity cannot be over emphasized (Ampatzoglou et
al.,2019).
Threats to External Validity
Creswell (2014) describes issues that arise when incorrect inferences are drawn
from research findings to other persons, settings, and or past or future situations as threats
to external validity. These threats could affect the ability to generalize the results of a
study questioning if this study will be relevant to others (Ampatzoglou et al., 2019).
External threats to validity are often placed in two categories: those related to the
populations used and those related to the environment in which the study takes place.
Caution was used when generalizing findings from a population sample in a
single setting to the whole population. This study used a sample of prelicensure nursing
students in a small community college in the southeastern United States. This sample
may not be representative of the population of prelicensure nursing students in other

64
geographical regions or in programs for diploma, associate degree, and baccalaureate
nursing programs. The results of this study may not be generalizable to other populations
of prelicensure nursing students but will allow for a generalization to a smaller
population of prelicensure nursing students in associate degree programs.
Recommendations to replicate the study in a variety of settings was suggested. However,
the results may add to the existing body of knowledge of evidenced-based educational
strategies for the development of clinical reasoning.
Environmental or experiment-related threats to external validity may make it
difficult to replicate the study. Clear descriptions of variables and protocols with
adequate detail can help to alleviate experiment-related threats (Ampatzoglou et al.,
2019). Multiple interventions can cloud the effect of the intervention that is being
measured. By ensuring that only one intervention was used between the measurements
helped alleviate this external threat to validity. While I was using secondary data, I am
assured that only one intervention occurred between the pre and post measurements.
Other threats to external validity can include a Hawthorne effect where subjects know
they are being studied and can skew the results (Forister & Blessing, 2016). The use of
secondary data that has not been analyzed will allow for unbiased subjects. Another
potential threat to external validity can be cause by the involvement of the researcher in
the study. This is referred to the Rosenthal effect (Forister & Blessing, 2016). The use of
secondary data prevents any personal traits from the researcher affecting the study
results.

65
Threats to Internal Validity
Threats to internal validity are described as unintended factors or conditions that
could affect the results (Forister & Blessing, 2016). Internal validity verifies that the
study measures what it is intended to measure and that there is enough data to support the
conclusions (Ampatzoglou et al., 2019). There are several factors or conditions that could
threaten internal validity. Creswell (2014) identifies internal threats to validity as
instruments, procedures, treatments, or participant experiences that have the potential to
cause an incorrect interpretation of the results in regards to the population of the study.
A potential internal threat to validity is a change in the instrument, pretest and
posttest, impacting outcome scores. The use of the same instrument (Lasater’s clinical
judgment rubric) supported the study outcomes. Time can threaten the internal validity of
a study due to maturation, history, or attrition. All students in the simulation completed
the pre and postintervention evaluations. The timing of the pretest and posttest occurred
in the same day, minimizing the experimental mortality or attrition where participants
dropout of the study (Creswell, 2014; Forister & Blessing, 2016). However, the pre and
post assessments being on the same day, I was unable to conclude if the improvements in
clinical reasoning was retained over time. For this study I will use a convenience sample
of students enrolled in the last clinical lower-level course. The G* Power Analysis
suggested a sample of 34 participants. The sample available is approximately 100
students. Forty-two students were selected (a 20% increase of suggested sample size) to
ensure an adequate number of completed tools were available for evaluation. I checked
with Center for Quality Control to see if a random sample from the available participants

66
would increase validity. A confidentiality agreement was required for all students
participating in simulation experiences, minimizing any diffusion of intervention effect.
Threats to Construct or Statistical Validity
Construct validity looks at how effective the test or experiment was in measuring
what was intended (Ampatzoglou et al., 2019). Was the measurement or method
appropriate? The methodology involves a one group pre/post design that will effectively
measure the effect of the intervention of questioning. The Lasater clinical judgment
rubric supports the constructs necessary to measure the processes used in clinical
judgment or clinical reasoning (cite this). The Lasater clinical judgment rubric is rooted
in Tanner’s clinical judgment model, leaving a broad enough measurement to support the
development of clinical reasoning. The first three construct of Tanner’s clinical judgment
model looks at closely at the process of clinical reasoning. Specific open-ended questions
were used to encourage a deeper type of thinking in each construct of the theory.
Creswell (2014) identifies threats to conclusion validity when researchers make
inferences that are inaccurate based on the data due to insufficient statistical power or a
violation with statistical assumptions. There will be a sufficient number of participants to
achieve statistical power based on calculations from G* Power Analysis decreasing the
risk of conclusion validity (Faul, Erdfelder, Lang, & Buchner, 2007). The data collected
by the college was adequate to support the needed sample for this study.
Ampatzoglou et al. (2019) posited that conclusion validity refers to what degree
the conclusions reached are representative of the data collected. This is usually the result

67
of researcher bias. The minimize this risk, the researcher will use the Lasater clinical
judgment rubric for evaluating the participants’ responses on the clinical judgment tool.
Ethical Procedures
Utmost care was taken to protect the rights of the participants by using
deidentified secondary data. The study posed no risk to the participants who were part of
the intervention when it was implemented and their data will not include names or
identifiers that could place the students who participated in the original intervention at
risk. Permission was obtained from the Walden University’s IRB, as well as permission
from the Director of Health Sciences and the Dean of Instruction of the community
college prior to any data collection procedures being collected.
There was no need for informed consent since my study used retrospective data.
The Lasater clinical judgment rubrics had no identifiers beyond descriptive data and a
randomly assigned number. The study used a convenience sample of data from the
records of students enrolled in their last lower-level clinical course. The records used for
this retrospective study were taken from records of students who were required to
participate in the simulation experience as a portion of their clinical experiences for the
clinical course. Each student was given the same amount of time to complete the research
instrument pre and postintervention. Since the study used retrospective data, the was no
influence on the students’ grade. All clinical judgment rubrics were scanned and will be
kept with analysis of all data in a secure, password protected computer, in a personal
location for five years.

68
Summary
Clinical reasoning is needed to make sound clinical judgements and obtain
optimal patient outcomes. It is important to have empirical evidence on teaching/learning
strategies that foster the development of clinical reasoning in prelicensure nursing
students. The quasi-experimental, one group post ex facto design will explore a sample
population of prelicensure nursing students to help provide evidence for the use of
questioning as an effective educational strategy in the development of clinical reasoning.
Problem-based learning as a strategy to increase clinical reasoning is well
supported in the research with a significant gap in the specific teaching/learning strategies
for the development of clinical reasoning. Questioning is the most prominent problem-
based learning strategy. This research study can enhance the current body of knowledge
on educational strategies for the development of prelicensure nursing students. Chapter 3
provides a description of how the research will be conducted with Chapter 4 relating the
data collection, description of the intervention, results of the data analysis, presentation of
the statistical data obtained.

69
Chapter 4: Results
PBL is one of the most widely used learning methods to foster clinical reasoning.
However, there are few studies that look at the specific learning strategies of PBL on the
development of clinical reasoning. The purpose of the study was to investigate the
influence of questioning as a PBL strategy on clinical reasoning in prelicensure nursing
students. My research question and hypotheses were as follows.
RQ – Quantitative: To what extent does the use of questioning as a problem-
based learning strategy influence the development of clinical reasoning in
prelicensure nursing students?
H0: Questioning as a problem-based learning strategy has no influence on the
development of clinical reasoning in prelicensure nursing students.
Ha: Questioning as a problem-based learning strategy influences the development
of clinical reasoning in prelicensure nursing students.
In this chapter, I discuss methods used for data collection. This includes the time
frame for data collection as well as any discrepancies in the data from the plan presented
in Chapter 3. Baseline descriptive data and demographic characteristics are discussed.
This is a representative sample of a larger population as discussed in terms of external
validity. Also presented are the results of the data followed by a summary.
Data Collection
Time Frame and Discrepancies
A request to use the 2017-2019 retrospective data from a simulation experience
already incorporated in the curriculum was approved by the Director of Health Sciences

70
and the Dean of Instruction since the community college had no formal IRB. Approval
was also obtained from Walden University’s IRB prior to recruitment. The college
provided the data as clinical judgment forms for both preintervention and
postintervention. The clinical judgment tools were evaluated using the LCJR. To verify
the consistency in my evaluation of the forms, I reevaluated the clinical judgment tools
using the LCJR after waiting 2 weeks from the initial evaluation. The results of the two
evaluations were exactly the same.
Descriptive and Demographic Characteristics of the Sample
The data were collected from a single simulation that was repeated in the clinical
course for 3 consecutive years. The period of time was selected to ensure an adequate
number of completed pre and postintervention clinical judgment tool sets were accessible
for analysis. Based on the G*Power calculation, a sample size of 34 was needed. I was
able to collect a total of 35 completed sets of clinical judgment tools for evaluation using
the LCJR.
This 8-hour simulation was part of the students’ required clinical experiences for
the course. The clinical judgment forms allowed the students to demonstrate their clinical
judgment ability and development (Adamson, et al., 2012). The LCJR allowed for a
measurement of the demonstrated ability and development prior to the use of questioning
by the instructor and after the use of questioning. Demonstrated ability and development
was demonstrated by the improvement of the total clinical judgment scores based on the
LCJR. There were no discrepancies from the original plan identified in the data
collection.

71
The sample consisted of the records of three cohorts of prelicensure ADN nursing
students enrolled between 2017 and 2019 in the clinical course. All students enrolled in
the course were required to have completed a pre and a post simulation clinical judgment
tool which was used for the analysis for this current study. The LCJR (pre and
postintervention) used by each student was assigned unique identifier so that the pre and
post tools were linked together by a single identifier. The dataset used for the sample for
this study consisted of a total of 35 completed clinical judgement tool sets. The LCJR
contained no identifiers beyond a number and the demographic information needed for
the study.
Representativeness
The sample was obtained from the larger population of ADN students in a small
community college in the southeastern United States. The sample included five males and
30 females as shown in Table 1. The sample may not be representative of the population
of prelicensure nursing students in other geographical regions or in other types of nursing
programs but allowed for a generalization to similar prelicensure nursing students in
associate nursing programs in the southeastern United States. Students ranged in age
from 21 years of age to 39 years of age with a mean age of 28.43 years of age.
Table 1
Demographic Information: Gender Formatting
n
Percent
Male
5
14.3
Female
30
85.7
Total
35
100.0

72
Results
Statistical Assumptions
According to Grove, et al, 2013, results from the general population have a
tendency to follow a normal distribution or a bell curve. However, testing for
assumptions are important to assure the robustness of any parametric test including the
paired t test. There are three assumptions for the paired t test (Forister & Blessing, 2016;
Grove, et al, 2013). First, the two sets of data must be collected from the same group. The
assumption was met as the two samples, pre and post, were paired with each participant
providing a pre and a postscore. The difference between the group scores must then be
tested to assure they follow a normal distribution and have no significant outliers (Grove,
et al, 2013). I had to first compute the difference between the pre and postintervention
scores to create a new variable for measurement. I used a histogram (see Figure 4) and
frequency chart to view the distribution of the differences and saw no visible differences
in normality or significant outliers in the difference scores between the two paired groups
indicating that the assumptions were met.
Because the sample size was less than 50, I then examined the intervention LCJT
difference score results for normality using the Shapiro-Wilks test to compare the
difference between the scores in the sample population to normally distributed scores
with the same mean and standard deviation (Fields, 2017). The Shapiro-Wilk test is used
to test normality when the sample population is smaller than 50 (Ghasemi & Zahedias,
2012). The results of the Shapiro-Wilk test (p = 0.105) were not significant (p < 0.05)
indicating that the paired t-test LCJT difference scores did not differ significantly from

73
the normal distribution (see Table 3). To further examine normality the distribution was
examined to see how far the difference scores were from 0 so the distribution for kurtosis
(-.448) and skewness (-.271) with neither result greater than +1.0 indicating little
deviation from normality (Fields, 2017).
For the third and final assumption of the t test, the differences between the paired
scores must be independent. Because each score represented the difference between the
paired individual groups, the final assumption for the paired t test was therefore met.
Table 2
Tests of Normality
Shapiro-Wilk
Statistic
df
Sig.
Difference in LCJT Pre and
Postintervention
.969
35
.416
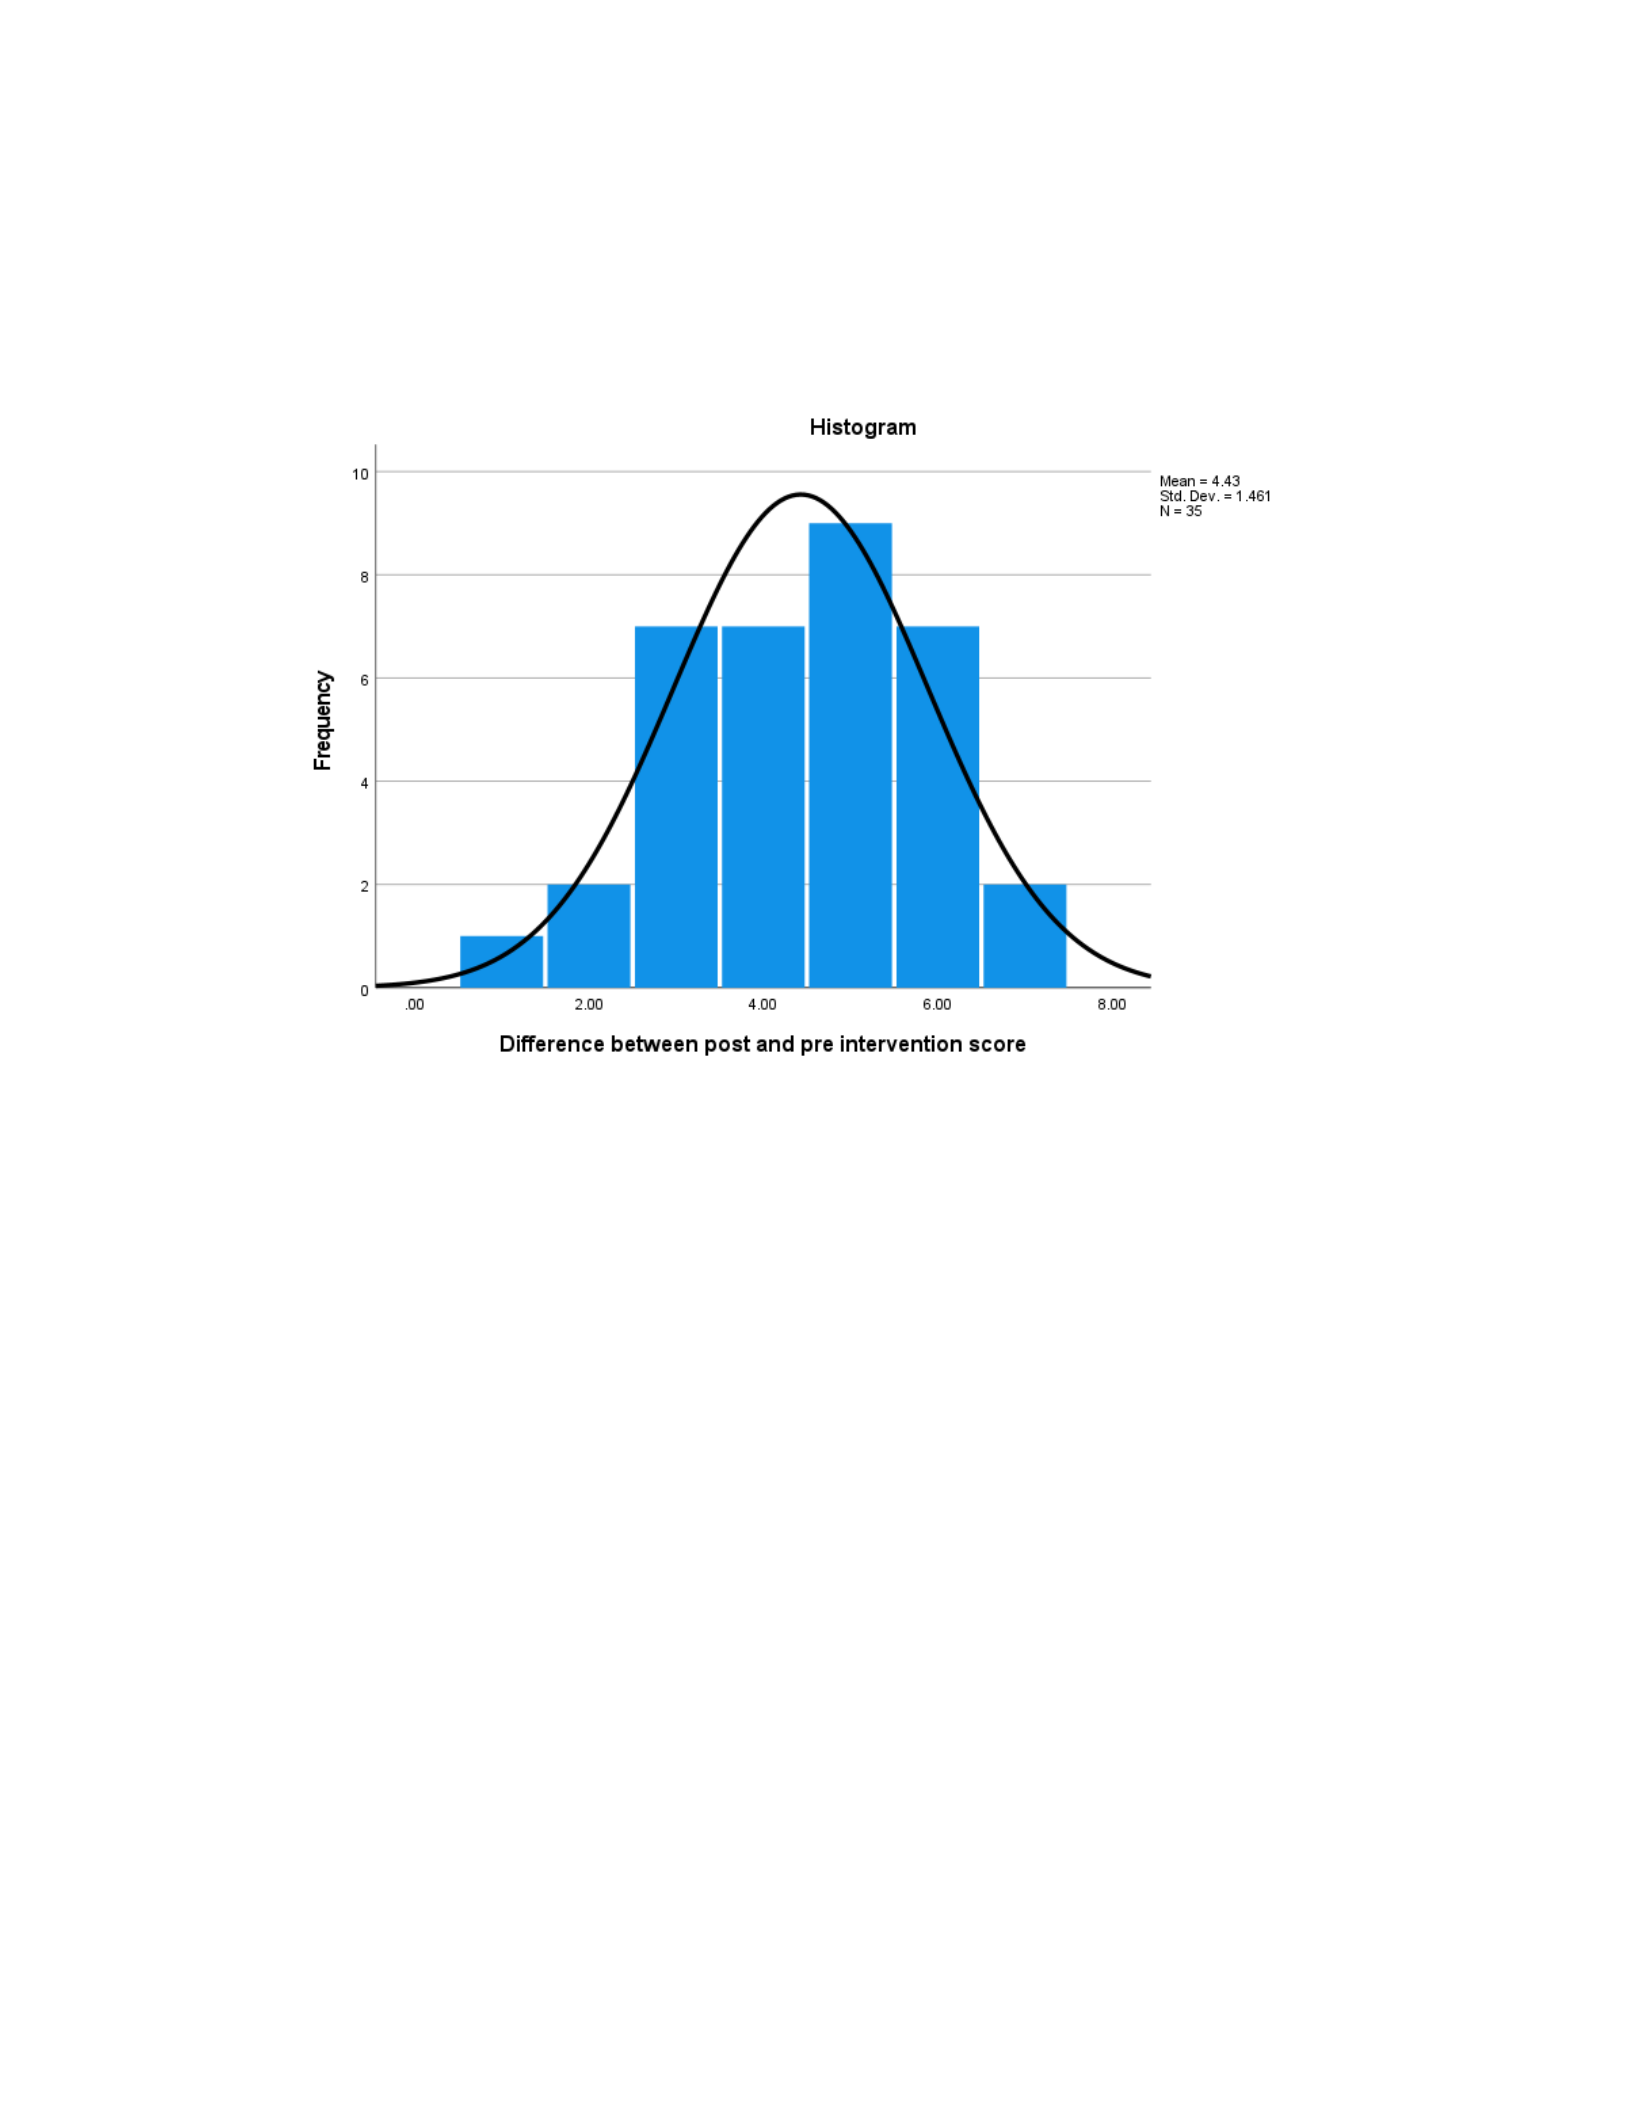
74
Figure 4
Difference in Pre and Postintervention Scores
Statistical Analysis
The pre-intervention score was measured immediately before the intervention and
the postintervention score was measured after the intervention and repeat of the
simulation and because the tests for assumptions of the paired t test were conducted and
all assumptions were confirmed as met, I proceeded with examining the results of the
paired t- test.
The paired t test was used to compare the means for the preintervention score (M
= 26.57, SD = 3.432) and postintervention score (M = 31.00, SD = 3.106; see Table 2).
The 35 participants had an average difference from preintervention LCJT scores to
postintervention LCJT score of 4.43 (SD = 3.106, 95% CI = [-3.817, -2.237], p <0.000),

75
indicating an increase in clinical reasoning. The correlation between the pre and
postintervention of questioning results was strong (r = .905, p <.001).
Table 3
Paired Samples Differences
95% CI of
Difference
Mean
Std.
Deviation
Std.
Error
Mean
Lower
Upper
t
df
p
Total LCJT
Score
Postintervention
-Total LCJT
Score
4.429
1.461
.247
3.927
4.930
17.933
34
<.001
I further examined the instrument’s internal consistency or reliability by running a
Cronbach’s alpha (.836), indicating a strong internal reliability coefficient (Grove et al.,
2013). Internal consistency or reliability is usually stronger with instruments that have
over 20 or more items. Since this instrument has only 11 items it was important to look
at internal consistency or reliability.

76
Table 4
Clinical Judgment Scores Pre and Postintervention Paired Differences
95% Confidence
Interval of the
Difference
Mean
SD
Std.
Error
Mean
Lower
Upper
t
df
Sig-
two
tailed
Pair 1
Focused observations –
Focused observations
postintervention
-.257
.443
.075
-.409
-.105
-3.431
34
.002
Pair 2
Recognizing deviations
from expected patterns –
recognizing deviation
from expected patterns
postintervention
-.486
.507
.086
-.660
-.312
-5.667
34
.000
Pair 3
Information seeking –
Information seeking
postintervention
-.714
.458
.077
-.872
-.557
-9.220
34
.000
Pair 4
Prioritizing data –
Prioritizing data
postintervention
-.457
.505
.085
-.631
-.284
-5.351
34
.000
Pair 5
Making sense of data –
Making sense of data
postintervention
-.514
.507
.086
-.688
-.340
-6.000
34
.000
Pair 6
Calm, confident manner –
calm confident manner
postintervention
-.171
.382
0.65
-.303
-.040
-2.652
34
.012
Pair 7
Clear communication –
Clear communication
postintervention
-.486
.507
.086
-.660
-.312
-5.667
34
.000
Pair 8
Well-planned
intervention/flexibility –
Well-planned
intervention/flexibility
postintervention
-.286
.458
.007
-.443
-.128
-3.688
34
.001
Pair 9
Being skillful – Being
skillful postintervention
-.171
.382
.065
-.303
-.040
-2.652
34
.012
Pair 10
Evaluation/self-analysis –
Evaluation/self-analysis
postintervention
-.571
.502
.085
-.744
-.399
-6.733
34
.000
Pair 11
Commitment to
improvement –
commitment to
improvement
postintervention
-.314
.417
.080
-.476
-.152
-3.948
34
.000
Pair 12
Total LCJT Score -Total
LCJT
Score Postintervention
-4.429
1.461
.247
-4.930
-3.927
-17.933
34
.000

77
The preintervention and postintervention scored reflected the scores obtained by
the students in the 11 areas of the Lasater clinical judgment rubric. Those 11 areas
represent the four components of Tanner’s clinical judgment model of noticing,
interpreting, responding, and reflecting. Each component of Tanner’s clinical judgment
model is reflective of clinical reasoning. All 11 areas showed significant improvements
on postintervention scores (see Table 4). The resulted t of 17.933 exceeds the critical t
value making the paired t test statistically significant demonstrating a definite difference
in the pre and postintervention values. This allows me to reject the null hypothesis that
questioning as a problem-based learning strategy has no influence on the development of
clinical reasoning in prelicensure nursing students.
Summary
The purpose of this study was to investigate the influence of questioning as a
problem-based learning strategy on clinical reasoning in prelicensure nursing students
using retrospective data from a nursing program. All assumptions surrounding the paired
t test were met for the research question. The null hypothesis was rejected when the t
exceeded the critical t making the t test statistically significant. Therefore, the hypothesis
that questioning as a problem-based learning strategy influences the development of
clinical reasoning in prelicensure nursing students is true.
In Chapter 5, I will address the results of this study and to what extent these
findings will have on the knowledge of nursing as a discipline. The implications of the
results will be discussed as they relate to positive social change. There will be one final
reflection on the knowledge obtained and the recommendations for further research.

78
Chapter 5: Discussion, Conclusions, and Recommendations
Clinical reasoning is the basis for every decision made by nurses. Those decisions
or clinical judgments will have a profound impact on patient care outcomes. Nurses with
sound clinical reasoning skills have a positive impact on patient outcomes while those
with poor reasoning skills may result in adverse patient outcomes (Billings & Halstead,
2016). For this reason, clinical reasoning and judgment are essential end of program
outcomes for prelicensure nursing students (Bussard, 2018; Tyo & McCurry, 2019).
The purpose of this study was to investigate the influence of questioning as a PBL
strategy on clinical reasoning in prelicensure nursing students. I used a paired t test to
analyze data collected. Results demonstrated a significant increase in clinical judgment
with the use of a series of questions to stimulate a more complex reasoning process in
clinical judgment. In this final chapter, I analyze and interpret the findings in the context
of Tanner’s clinical judgment model using the LCJR. Tanner’s clinical judgment model
is the foundation of many studies on clinical reasoning and clinical judgment (Ashley &
Stamp, 2014; Bussard, 2015; Jessee & Tanner, 2016; Monagle et al., 2018). I discuss
limitations of the study, describe recommendations for future research, and discuss the
potential impact of the study on positive social change.
Interpretation of the Findings
The findings of this study came to the same conclusion as the 2013 Shin and Kim
study that PBL in nursing had a positive effect on development of clinical reasoning in
the education of nurses. This study focused on the problem-based teaching/learning
strategy of questioning. Students showed an increase on the assessment scores from

79
preintervention (questioning) to postintervention by a mean of 4.43 points. This
improvement was demonstrated not only in clinical judgment but also in clinical
reasoning. Clinical reasoning is the complex decision making the process that uses
nursing knowledge and several methods of thinking in order to make clinical judgments
(Tyo & McCurry, 2019). It is where the students gather and analyze data or cues,
determine the relevance of the information, and look for interventions that could improve
patient outcomes (Vallente, 2016).
With the pre and postassessments being on the same day, I was unable to
determine if the improvements in clinical reasoning were retained over time. Students
uncover their clinical reasoning skills by observing their instructors thought processes
then applying them in the same simulation (Lasater, et al., 2014). Other problem-based
strategies that had previously been studied are case studies and clinical scenarios, web-
based case studies, collaborative learning, concept mapping, experiential or clinical
practicum, reflective journaling, and simulation. To add to the body of knowledge on
developing clinical reasoning, I chose to study questioning and its influence on clinical
reasoning in the prelicensure nursing student.
The LCJR was used to measure the clinical judgment tools (Appendix A) that
served as the preintervention and postintervention assessment. Gonzalez (2018) posited
that the LCJR is an effective tool for evaluating clinical reasoning skills. The LCJR has
also successfully been used to evaluate clinical judgment behaviors in the clinical setting
(Kavanagh & Szweda, 2017; Manetti, 2018; Nielson et al., 2016). Success was
demonstrated in each of these studies using the LCJR to teach clinical reasoning and

80
judgment. A paired t test was used to measure differences in the students’ clinical
reasoning ability prior to and after the introduction of the intervention of questioning. In
this current study, all students showed an increase in postintervention scores using the
LCJR. The LCJR (Appendix B) has 11 behavioral components based on the four
performance aspects of Tanner’s clinical judgment model: noticing, interpreting,
responding, and reflecting making it closely aligned with the theoretical framework of
this study (Lasater, 2011).
Limitations of the Study
Limitations are present in most research studies. This study was no exception. I
identified three limitations. The first use the use of a convenience sample which does not
allow the study to be generalized to a larger population. The second limitation was the
fact that there was no way of knowing whether clinical reasoning was impacted by
previous experience, knowledge, or skill. The comparison of a preintervention and
postintervention should allow for a determination of growth regardless of the student’s
starting point. However, with the age range of 21-39, students came into the program
with different levels of reasoning based on previous experiences. The postintervention
assessment was completed after the intervention and repeat of the simulation. With such a
short time between evaluations, there is a possibility that some students may have
memorized important reasoning processes. Having the students utilize their reasoning
skills in the repeat simulation would have minimized the limitation. The last limitation
identified was time. The study evaluated retrospective data from nursing students in a
clinical course over several sections of the course. This snapshot in time is dependent

81
upon conditions at that time. While the students showed improvement after the
intervention of questioning, there is no way to determine whether the student would
retain their improved reasoning skills over time.
Recommendations
It is recommended that additional research be conducted on the various
educational strategies that could potentially influence clinical reasoning and judgment to
boost this body of knowledge. Nurse educators need evidenced-based educational
strategies as they prepare their students to navigate complex healthcare problems.
Clinical judgment and the process of clinical reasoning is the goal to providing effective
and safe nursing care (Brenton, 2018; NSCBN, 2019). The fact that 50% of medical
errors involve a new nurse, with 65% of those errors involving some lapse of clinical
judgment is unacceptable (Brenton, 2018; NCSBN, 2019).
I would recommend a repeat of this study using a larger randomized sample. This
could allow for a generalization to the larger population of prelicensure nursing students.
In addition, comparison of different age groups and students with previous careers could
add additional validity to the study. A longitudinal study, including an additional
measurement of postintervention at various intervals throughout the nursing program,
would help to determine if the improved reasoning skills are retained over time.
Implications
The mission of Walden University is to transform career practitioners into
scholar-practitioners who can effect positive social change (Walden University, 2021).
This study may promote positive social change as the results will help fill the gap in the

82
literature by providing research results on an individual problem-based educational
strategy to assist similar educational programs in the development of clinical reasoning.
The goal of problem-based learning is to improve reasoning skills and solving real life
problems (Breytenbach, et al, 2017; Wosinski, et al, 2018). The use of evidenced-based
learning strategies to promote clinical reasoning in nursing students supports the new
graduate to make better clinical judgments as they transition into practice making it
critical to achieving desirable patient outcomes (Kavanagh & Szweda, 2017). Students
with sound clinical reasoning skills are more practice ready, have more confidence, and
transition as new graduates into practice more easily (Parker, et al, 2014).
Nurse Educators may also be impacted. The use of evidenced-based
teaching/learning strategies give nurse educators the tools to effectively impact the
knowledge, skills, and attitudes of nursing students in their development of clinical
reasoning. Robeznieks (2015) reported that the New York-based Jonas Center for
Nursing Excellence estimates that each nurse educator has the potential to affect the care
of 3.6 million patients. This number was based on the number of nurses each instructor
could teach throughout their career along with the number of patients for whom those
nurses could provide care throughout their career. Improving the clinical reasoning skills
of nursing students truly effects millions of patients. Better patient outcomes will have
the potential to reduce inpatient length of stay with more efficient care. More efficient
and safe care can lead to savings in resources and dollars for healthcare in general.
Practice ready new graduates have the potential to decrease orientation costs of
new graduates. The readiness of new graduates to enter the workforce is an international

83
concern creating not only the necessity of longer orientation programs, but many
hospitals have added extended residency programs for new graduate support (Baumann,
Hunsberger, Crea-Arsenio, & Askar-Danesh, 2017; Parker et al., 2014).
Conclusion
There is a great concern over the facts that 50% of medical errors involve a new
nurse with 65% of errors involving a lapse of clinical judgment (Brenton, 2018; NCSBN,
2019). Another area of concern is that only 23 % of new graduate nurses are safely able
to recognize problems due to urgent changes in patient condition and demonstrate
appropriate management of those problems (Kavanaugh & Szweda, 2017). Finding ways
to develop clinical reasoning skills in prelicensure nursing students is key to helping
graduate nurses make sound clinical judgment. The findings of this study indicated that
the use of questioning had a positive effect on the development of clinical reasoning in
prelicensure nursing students as every student showed an increase in the LCJR scores
postintervention. Increasing clinical reasoning and judgment skills in nursing students
will help them recognize patient cues (noticing), analyze patient data (interpreting),
generating solutions and taking action (responding), and evaluation (reflection)
completing Tanner’s clinical judgment model.
The benefit to nurse educators cannot be overlooked. As nurse educators look for
evidenced-based educational strategies to help them facilitate the development of clinical
reason in their students, this study will provide an additional strategy for consideration,
taking them one step closer to graduating practice ready nurses.

