


INTRODUCTION Traffic fatalities account for an astonishing
Background
Traffic fatalities account for an astonishing 1.24 million deaths per year
worldwide (Global Status Report on Road Safety, 2013). In the United States nearly
33 thousand lives were lost in motor vehicle crashes (“Traffic Safety Facts,” 2014).
These alarming statistics are coupled with the economic costs of motor vehicle
crashes, which in 2010 were an estimated $277 billion in the United States
(Economic and Societal Impact of Motor Vehicle Crashes, 2014). These statistics
leave no wonder as to why safety is of the utmost importance in all transportation
sectors. Safety is a complicated issue with many interrelated factors which affect
the safety of a roadway network. With the complete understanding that there are
several factors not explored in this thesis, the focus is mostly on risk-taking
behavior as a construct to fatality rates. Many studies have been performed to
distinguish the factors associated with the variation in safety measures throughout
the United States and the world. The southeastern region of the U.S. stands out for
having some of the highest rates of injury and fatality crashes per capita, which has
led to several studies that try to explain the unsafe anomalies associated with the
southeastern region. The majority of previous studies have focused on physical
design of infrastructure, weather, government policies, and socio-demographic
factors such as gender, age, race and ethnicity; such as: “Stop Sign Violations: The
role of race and ethnicity on fatal crashes,” by Romano, Voas and Tippetts, which
describes the role of race/ethnicity in fatal crashes, “Analyzing Road Safety in the
United States,” by Oster and Strong, which reviews the road safety performance in
theU.S., “Injury Severity of Multivehicle Crash in Rainy Weather,” by Jung, Qin, and

Noyce, which studied effects of rainy weather on injury severity of crashes, and “A
call to Safety,” by Heller, which addresses issues about distracted driving policies in
the U.S. All of the issues from previous studies are important and have significant
impacts on the safety of the roadway network. However, this thesis is different in
that the focus is on risk-taking behaviors, cultural factors, and health factors
associated with the socio-demographic characteristics as possible explanatory
factors in the variation of fatality rates in the southeastern region of the U.S.
There are several definitions of risk-taking behavior available. Risk taking
behavior is defined as, “any consciously, or non-consciously controlled behavior with
a perceived uncertainty about its outcome, and/or about its possible benefits or
costs for the physical, economic, or psycho-social well-being of oneself or others
(Trimpop, 1994).” Another definition of risk-taking behavior is “the tendency to
engage in behaviors that have the potential to be harmful or dangerous, yet at the
same time provide the opportunity for some kind of outcome that can be perceived
as positive (Tull, 2014).” Yet another alternative definition of risk-taking behavior is
the actions of a person when facing the possibility of physical, social, or financial
harm due to a hazard, uncertainty in outcomes, or to seek feelings of excitement
(Rohrmann, 2002). The risk-taking driving behaviors that are being referred to in
this thesis are the unhealthy risk-taking driving behaviors, some of which are
avoidable choices, and some of which are often unavoidable such as driving to work
in adverse weather, or driving home in the dark. The idea that an individual is more
likely to engage in risky driving behaviors if they are willing to engage in other
unhealthy risk-taking behavior in their life decisions comes from the idea that each
type of risk is associated with the individual’s perception of their self-worth, self-

esteem, and confidence (McLeod, S.A., 2012). Examples of other risky behavior in
life decisions are the choice to smoke, drink alcohol, use illicit drugs, drop out of
school, recklessly take out lines of credit that are nearly impossible to repay given
the individuals financial situation, etc.
Some of the risk-taking, cultural, and health factors that were initially
explored in this research include credit scores, seat belt use, education levels,
poverty and homelessness levels, alcohol consumption, drug and tobacco use,
obesity, overall general health, and depression and other mental health issues
causing diminished cognitive capabilities. Road use factors which were considered
include share of tourists and visitors, vehicle occupancy levels, lighting condition of
fatal crashes, average age of vehicles, and land use patterns. Through the
exploration of the data available at both aggregate and disaggregate levels, many
of the above mentioned factors were found to have correlations with fatality rates at
the state and regional levels, suggesting that understanding these different
characteristics of the population by geographical region can help to determine,
explain, and potentially provide insight regarding how to improve the safety of the
roadway network for personal vehicle travel.
The idea in correlating risk-taking behavior with fatality rates comes from the
assumption that individuals who have a higher likelihood of performing risky
behavior in some aspects of their life are also more likely to display risk-taking
behaviors while driving or as pedestrians. Risk-taking behavior while driving is
referring to aggressive driving characteristics such as: speeding, reactionary lane
changing without proper notification or attention, tailgating, hard braking, etc. The
National Highway Traffic Safety Administration (NHTSA) defines the occurrence of

aggressive driving as “an individual commits a combination of moving traffic
offenses so as to endanger other persons or property (NHTSA.gov).” Other risk
taking behavior while driving could include distracted driving, drowsy driving,
impaired driving, lack of use of safety equipment while driving such as safety belt
use, helmet use for motorcycle drivers, or improper or lack of car seat use for
children and infants (Research & Evaluation, 2014). In addition, risk-taking might
include activities such as driving in inclement weather and in poor road conditions,
driving a vehicle in need of maintenance, or allowing oneself to be distracted while
driving, etc. Similarly, behaviors of pedestrians, bicyclists, and motorcyclists can
include risk-taking elements.
1.2 Introductory Note
Vehicular crash rates and fatality rates are consistently higher in the
southeastern U.S. than the national average as shown in the Fatality Analysis
Reporting System. In addition, pedestrian fatality rates are also consistently higher
in the southeastern U.S. than the national average (Dangerous by Design, 2014).
With safety as a top priority in all sectors of transportation, it is imperative that the
safety of the roadway network in the southeastern region of the U.S. is improved.
To improve the safety of the roadway network, the factors associated with the lack of
safety in the region must be identified and addressed. Transportation safety is an
extremely complicated subject matter with an enormous number of interrelated
factors which influence safety as a whole. If transportation network safety were an
easy issue to address, or if safety was a straightforward problem with a singular best
answer, then solutions would be readily available. With the understanding of the

complicated nature of the problem of safety, this thesis focuses on just one aspect,
risk-taking characteristics. In order to identify the possible explanatory factors
involved with the lack of safety on the southeastern U.S. roadway network, risk-
taking characteristics are being explored, which were previously not evaluated as
conventional factors associated with safety.
1.3 Southeastern Transportation Center
The Southeastern Transportation Center (STC) is a consortium focused on
comprehensive transportation safety and is comprised of nine universities in the
southeastern U.S. The University of Tennessee is the lead institution which is home
to the director and co-director. The other universities include: the University of
Central Florida, University of Alabama, University of Alabama Birmingham,
University of Kentucky, North Carolina A&T State University, University of North
Carolina – Chapel Hill, and Clemson University. It is important to note that the
regions referred to are in accordance with U.S. Department of Transportation’s
(DOT) definitions of regions, not the U.S. Census Bureau’s definition of regions. The
DOT defines region four of the U.S. as Alabama, Florida, Georgia, Kentucky,
Mississippi, North Carolina, South Carolina, and Tennessee. In 2010, each of the
states in the southeastern region had higher fatality rates than the national average
both in terms of per capita and per vehicle miles of travel, and half of the
southeastern states ranked in the top ten of overall fatalities per capita, however as
of 2012, the number of southeastern states ranked in the top ten dropped to only
three, but there is still plenty of room for improvement (Southeastern
Transportation Center, 2015).

This thesis is part of a study being carried out by the University of South
Florida in collaboration with the University of Tennessee and the University of
Alabama, each of whom have various tasks exploring the relationship between
risktaking factors and travel safety. This thesis is representative of just one part of
the efforts being carried out by the University of South Florida.
1.4 Objective
The objective of this thesis is to explain the variation of fatality rates in the
southeastern region of the U.S. using different risk-taking characteristics as
explanatory variables in addition to several socio-demographic characteristics
known to effect driving behavior. The hypothesis being tested is that if the average
population in a specific geographical area behaves in a risky manner as a whole in
economic and health impacting characteristics that the same population may also
behave in a risky manner while operating a motor vehicle or using the roadway
network in other manners such as walking or biking. In other words, if an individual
is willing to take a given type of risk, they are inherently more likely to take
multiple risks, not just a singular risk. The hypothesis, restated is that if a person
exhibits risk-taking behavior, that risk-taking behavior is likely not limited to only
one aspect of risk, but is likely to occur in multiple facets of the person’s life.
1.5 Outline
This thesis gives an overall literature review comparing the variation of
fatality rates in the United States (U.S.) and the rest of the world for completeness,
then focuses on the variation of fatality rates in the southeastern region of the U.S.
compared to the rest of the nation. Following the fatality rate review, the different

risk-taking characteristics explored are reviewed. The methodology data collection
and analysis follows the literature review. In the fourth chapter of the thesis, the
data collection and analysis is reviewed, and the proposed regression model to
estimate fatality rates by geography and risk-taking characteristics is introduced.
The final chapter, chapter five, contains the conclusions and the suggestions for
future research regarding the topic of risk-taking variables as explanatory factors in
estimating fatality rates by geography.
CHAPTER 2:
LITERATURE REVIEW
The following literature review covers fatality rates, the variation of fatality rates by
geography, and the risk-taking behaviors that are proposed as explanatory factors
which affect the variation in fatality rates.
2.1 United States Compared to World’s Fatality Rates
Worldwide in 2010, 1.24 million people were killed in road traffic injuries,
which are estimated to be the eighth leading cause of death globally (Global Status
Report on Road Safety, 2013). The World Health Organization (WHO) reported that
road traffic fatality rates vary from 24.1 per 100,000 population in the African
Region, to 10.3 per 100,000 population in the European Region. The U.S.

experienced an 11.4 per 100,000 population traffic fatality rate in 2010. The
statistics show that the middle-income countries have the highest road traffic
fatality rates at an average of 20.1 per 100,000 population, followed by low-income
countries at an average rate of 18.3 traffic fatalities per 100,000 population, and
high-income countries have among the lowest traffic fatality rates at an average of
8.7 per 100,000 population. This variation in fatality rates by income status is
related to the share of vulnerable road users in a country. Vulnerable road users
include pedestrians, bicyclists, motorcyclists, and other users of two- or
threewheeled vehicles. Low- and middle-income countries have a higher proportion
of vulnerable roadway users, due to the lower costs and higher availabilities of
these modes. The U.S. is categorized as a high-income country, however many of
the laws which help to reduce traffic fatality rates are at subnational levels, leaving
plenty of room for improvement in traffic safety. A national urban speed limit
suggested by the WHO is less than or equal to 50 kilometers per hour, which
converts to about 30 miles per hour, however is only implemented in 47% of the
world’s population. The U.S. is one of the only countries with motorcycle helmet
laws and seat-belt laws at subnational levels when compared to the rest of the
world.
Perhaps most alarming is the share of countries with child restraint laws in
place coupled with good law enforcement of these laws. Child restraint law
enforcement is yet another area where the U.S. is categorized at a subnational level
(Global Status Report on Road Safety, 2013). While the U.S. is not among the
highest traffic fatality rates in the world, there is plenty of room for improvement in
the safety of the roadway network in the U.S. With each of the above mentioned

safety measures, speed limit, helmet laws, seat belt laws, child restraint laws, etc.
high levels of enforcement and high perception of enforcement is key to ensuring
new and existing policies are as effective as possible.
Differences in infrastructure conditions among countries also have great
influences on the safety variations of the networks. Road design, engineering,
construction, and maintenance are all influences to the safety of the roadway users
for all modes. According to the WHO, 77 percent of countries already carry out
some type of road safety audit on new road infrastructure, however existing
infrastructure also needs to be inspected with focuses on high risk, high incident
areas. In addition to infrastructure, typical vehicle age also plays a significant role
in the safety of a road network (Global Status Report on Road Safety, 2013).
Technology is improving tremendously with each passing year, and along with the
improved technology, the safety features in vehicles increase as well. With
increasing safety features such as multiple airbags, antilock brakes, and crushable
designs which allow the impact to be absorbed by the vehicle rather than the
occupant, the injury severity of motor vehicle crashes should reduce. This increase
in technology is often seen first in high-income countries where the population can
afford the luxuries of newer vehicles.
Emergency healthcare capacities are also a variable that plays a significant
role in the survivability of a person involved in a sever motor vehicle crash.
According to the WHO, as of 2013 only 59 countries have ambulatory services that
can rapidly transport the majority of patients to a hospital in the event of a crash.
In addition to the ambulatory services that are unavailable in many countries

around the world, the proportion of doctors and nurses that are trained to provide
emergency medical services range from less than 40 percent in the African and
South-East Asia regions to under 90 percent in the Eastern Mediterranean region.
In the region of the Americas, about half of nurses and over 70 percent of doctors
have this type of training (Global Status Report on Road Safety, 2013).
2.2 National Average Compared to Southeastern U.S.
Section 2.2 of this thesis focuses on the variation of characteristics between
the southeastern region of the nation and the rest of the nation, including fatality
rates and other characteristics that may affect fatality rates. The higher fatality
rates that occur in the southeastern region of the U.S. are a great motivation for
this study, and a phenomenon that should be researched thoroughly to improve the
safety of the southeastern U.S. population. The following table displays the fatality
rates in each state in the southeastern region, and the national average fatality
rate, in addition to the lowest and highest state in the nation.
Table 1 Fatality Rates in Southeastern Region
South Carolina
1.70
Mississippi
1.58
Kentucky
1.55
Tennessee
1.40
Alabama
1.35
Florida
1.26
North Carolina
1.23
Georgia
1.12
Total U.S.
1.11
D.C. (Lowest)
0.62
Montana (Highest)
1.74
Data Source: FARS and Census Bureau
2.2.1 Fatality Rates
U.S. roadways have experienced a reduction in fatalities of nearly 25 percent
between 2004 and 2013, however this still equated to almost 33 thousand motor
vehicle traffic crash deaths in 2013 (Traffic Safety Facts, 2014). The national
fatality rate in the U.S. is measured by exposure, thus is measured in fatalities per
100 million vehicle miles traveled (VMT) for most uses. In 2013, the U.S. fatality
rate was 1.10 per 100 million VMT, which constituted a 3.5 percent decrease in just
one year, and also ties for the lowest fatality rate on record for the nation (Traffic
Safety Facts, 2014). Just as recently as 2008, motor vehicle traffic crashes were
the number one cause of death for every age from 13 through 30 (Subramanian,
2012). The CDC reports fatality rates per population in the top 50 Metropolitan
Statistical Areas (MSA), and found that while overall, 74% of MSAs had traffic
fatality rates below the national average, the traffic fatality rates in the southern
states were generally higher. Furthermore, the highest vehicular fatality rates are
concentrated in the southeastern region of the U.S. (Motor Vehicle Crash Deaths in
Metropolitan Areas – United States, 2012). Pedestrian fatalities are another area of
concern, where the southeastern U.S. ranks higher than the national average in
fatalities. In 2012, pedestrians represented nearly 15 percent of all traffic fatalities
in the U.S. (Dangerous by Design, 2014). The share of traffic deaths involving
pedestrians in the U.S. has been an increasing trend from 2004 through 2013
(Dangerous by Design, 2014). Even more alarming is the overrepresentation of the
southeastern region of the U.S. when the top 50 metropolitan areas are ranked by
Pedestrian Danger Index (PDI) shown in Table 2. The PDI gives and approximation
of the likelihood of a person on foot being struck and killed by a vehicle based on
the best available measure of how many people are likely to be walking and the
number of pedestrian fatalities in the past five years of data. The states in the
southeastern U.S. account for eight of the top ten worst metropolitan areas, and
each of the top six are in the southeastern states. Florida is currently the worst
among the PDI rankings, home to the top four most dangerous metropolitan areas
for pedestrians (Dangerous by Design, 2014). These alarming pedestrian fatality
rates, and overall traffic crash fatality rates in the southeastern region of the U.S.
leads to the obvious question of why. Is it the demographics of the southeastern
U.S., the physical design, the governmental policies or lack thereof, the
environmental variations of the southeastern U.S. from the rest of the nation, or
maybe it is all of the above mentioned reasons and more that the southeastern U.S.
has such alarming fatality rates.
Table 2 Pedestrian Danger Index Ranks in Southeastern Region
Rank
Metro Area
PDI
1
Orlando-Kissimmee, FL
244.28
2
Tampa-St. Petersburg Clearwater, FL
190.13
3
Jacksonville, FL
182.71
4
Miami-Fort Lauderdale-Pompano Beach, FL
145.33
5
Memphis, TN-MS-AR
131.26
6
Birmingham-Hoover, AL
125.60
8
Atlanta-Sandy Springs-Marietta, GA
119.35
10
Charlotte-Gastonia-Concord, NC-SC
111.74

15
Nashville-Davidson Murfreesboro-Franklin, TN
100.79
16
Raleigh-Cary, NC
100.35
Data Source: Dangerous by Design, 2014
2.2.2 Demographics
Unfortunately, the higher than average fatality rates are not the only
characteristics that are present in the southeastern U.S. When the intergenerational
upward mobility of children was calculated based on the mobility of their parents it
was found that the southeastern region of the U.S. stands out very distinctly from
the rest of the country as being much less upwardly mobile than other regions of
the nation (Chetty, et. al., 2014). According to Chetty, et al. intergenerational
mobility is the degree to which a child’s social and economic opportunities are
dependent upon their parents’ social and economic status. The U.S. Census Bureau
also shows southeastern poverty levels to be among the highest in the nation, with
poverty shares of population ranging from more than 17 percent in Florida to nearly
24 percent in Mississippi (Small Area Income and Poverty Estimates, 2013). The
national share of population below the poverty line is less than 16 percent. This
thesis sets out to determine the varying socio-economic and socio-demographic
characteristics in the region that may help to explain why the fatality rates are
consistently above the national averages. The main argument defined is that
poverty is greatly correlated to propensity for risk taking behavior, and risk-taking
behavior is linked to driving characteristics that make the roadway network in the
southeastern U.S. inherently more dangerous.

The approximate 2013 population of the U.S. was 316 million people, of
which 23.3% were under 18 years of age, and 14.1% were over the age of 65,
leaving 62.6% of the population in the typical working adult age range (Census,
2013). As of 2013, 50.8% of the U.S. population was female. Racially the majority
of the U.S. was White, accounting for a 77.7% share of the population, followed by
13.2% Black or African American, 5.3% Asian, 1.2% American Indian, 0.2% Native
Hawaiian or other Pacific Islander, and 2.4% are two or more races. When the
average was taken over the past 5 years of data, from 2009 to 2013, 86.0% of the
U.S. population over age 25 was a high school graduate or higher, and 28.8% of
that same age group had a Bachelor’s degree or higher. From 2009 to 2013, the
average share of the population below poverty level was 15.4% (Census, 2013).
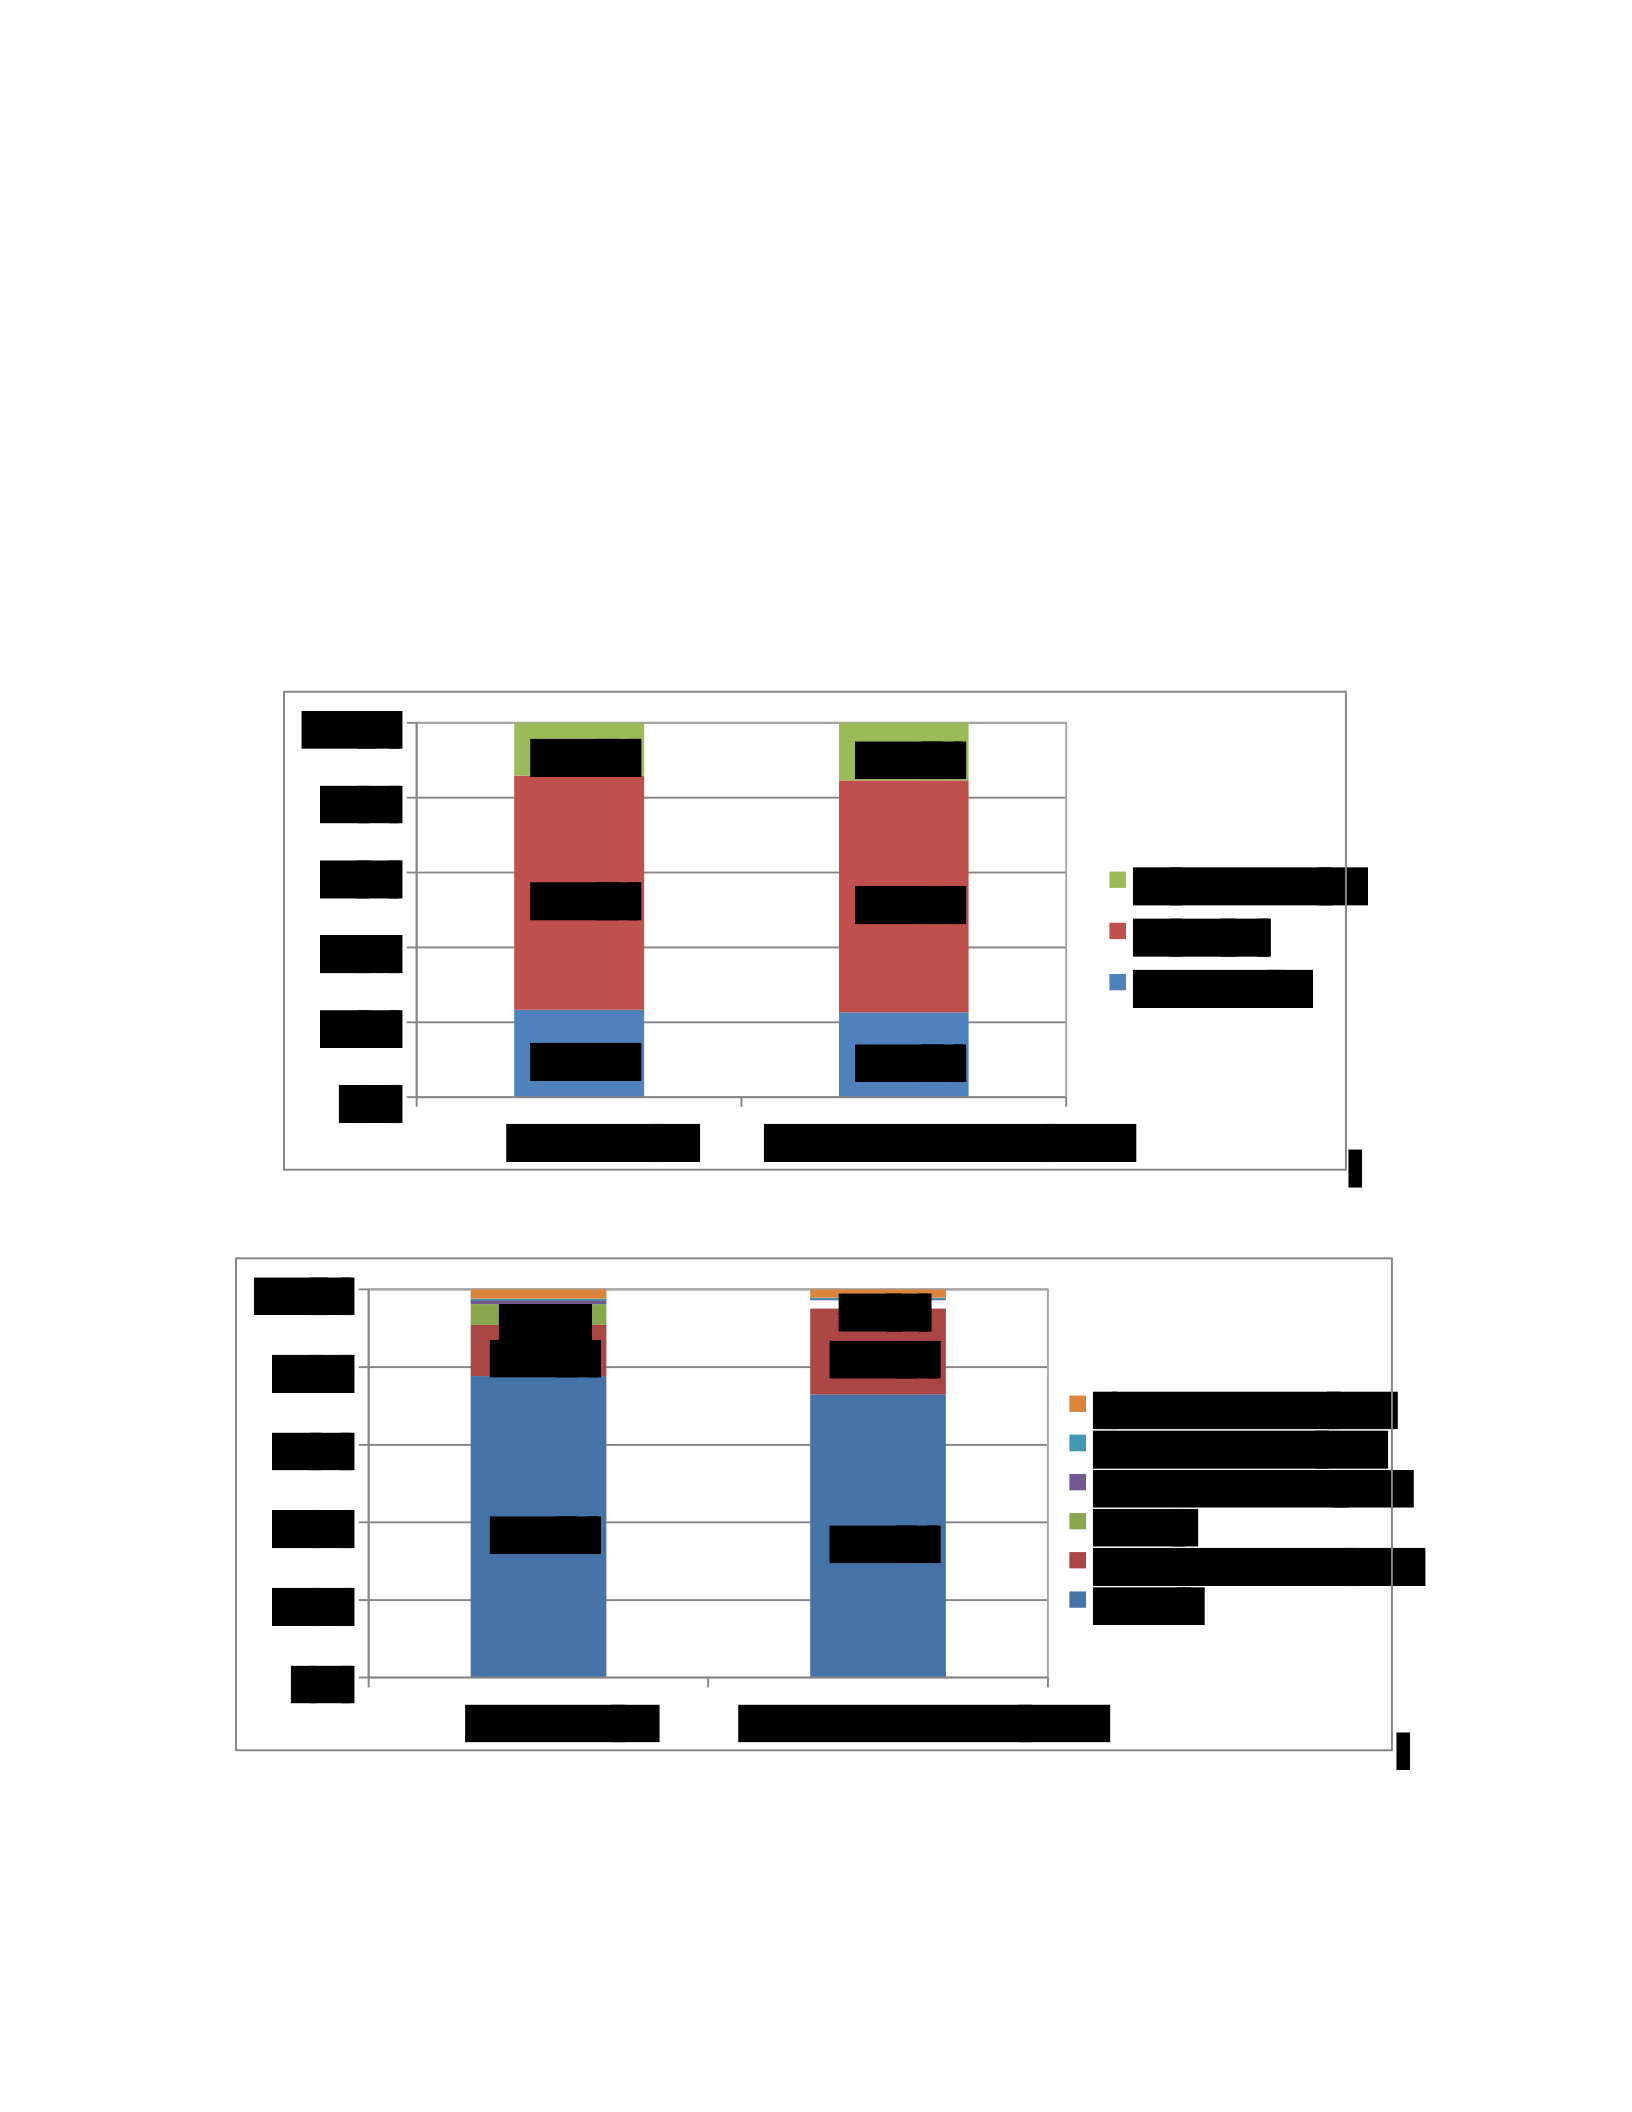
The approximate 2013 population of the southeastern U.S. was 63 million people,
of which 22.6% were under 18 years of age, and 15.4% were over the age of 65,
leaving 62.0% of the population in the typical working adult age range as shown in
Figure 1 (Census, 2013). As of 2013, 51.2% of the southeastern U.S. population
was female. Racially the majority of the southeastern U.S. population was White,
accounting for a 71.5% share of the population, followed by 21.6% Black or African
American, 2.2% Asian, 0.4% American Indian, less than one tenth of one percent
are Native Hawaiian or other Pacific Islander, and 2.1% were two or more races as
shown in Figure 2. Total shares of race do not add to 100 percent due to errors
associated with rounding. When the average was taken over the past 5 years of
data, from 2009 to 2013, 84.8% of the southeastern U.S. population over age 25
was a high school graduate or higher, and 25.5% of that same age group had a
Bachelor’s degree or higher as shown in Figure 3. From 2009 to 2013, the average
share of the southeastern population below poverty level was 17.7% (Census,
2013). In general, the southeastern U.S. has less working age adults, more young
people, more elderly, and a larger share of Black or African American population
than the rest of the nation. The southeastern states are also disproportionately less
educated, and have a larger share of the population below poverty than the
national average. Each of these demographic characteristics has an impact on the
general safety of the roadway network in the southeastern U.S.
Figure 1 Age Group Comparisons. Data Source: U.S. Census Bureau
Figure 2 Race Comparisons. Data Source: U.S. Census Bureau
%
23.3
22.6
%
62.6
%
62.0
%
14.1
%
15.4
%
0
%
%
20
%
40
60
%
%
80
%
100
Total U.S.
Southeastern U.S.
and older
65
to
64
18
Under 18
%
77.7
%
71.5
13.2
%
%
21.6
5.3
%
2.2
%
%
0
%
20
%
40
%
60
%
80
100
%
Total U.S.
Southeastern U.S.
or more races
2
Pacific Islander
American Indian
Asian
African American
White
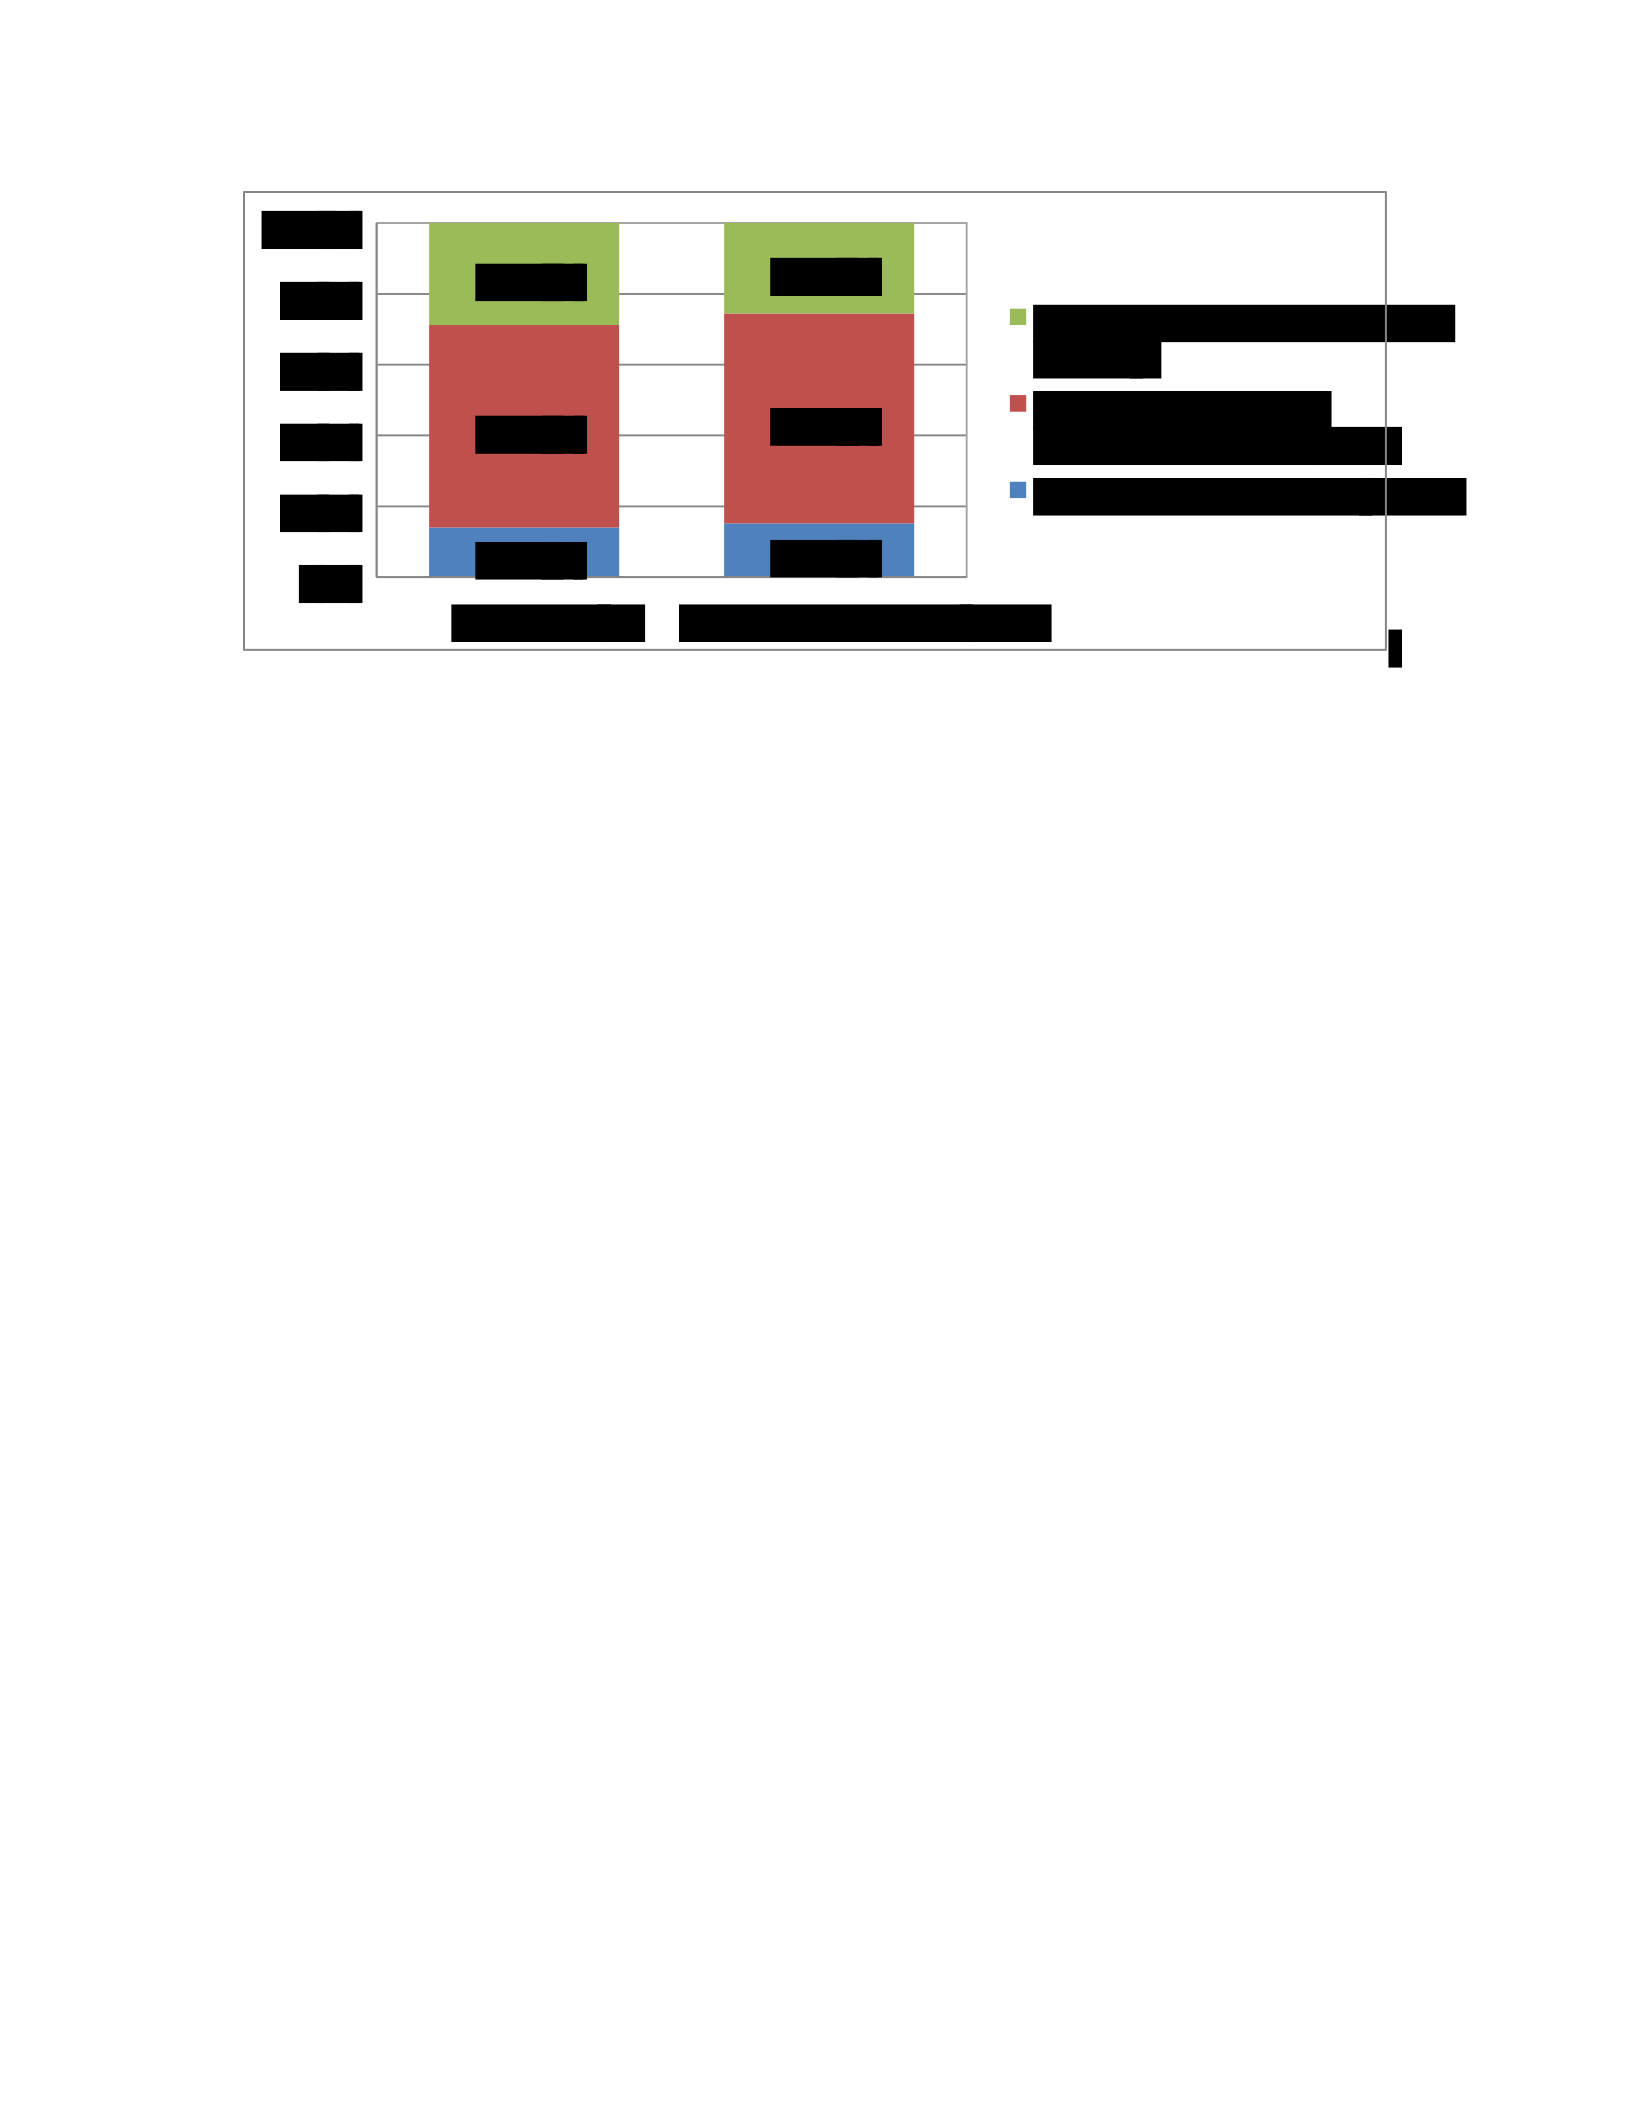
Figure 3 Education Comparisons. Data Source: U.S. Census Bureau
According to Polzin, demographics, more specifically race and ethnicity, have
been found to have strong distinctions in mode choice, and some mode choices are
distinctly safer than others. Hispanics are twice as likely to carpool as White
NonHispanics, and almost three times as likely to use transit to commute. Transit
commute share is the greatest among the Black population. Hispanics have the
highest commute share of bicycle travel, and Asians have the highest share of walk
as a commute mode choice (Polzin, et al., 2013). While this thesis focuses primarily
on fatality rates of the overall roadway network, it is important to understand the
connection between share of alternative mode users and the safety of a roadway
network. Vulnerable road users such as pedestrians and bicyclists experience the
highest risk when traveling on the roadway network. Non-motorists have the
inherent exposure risk, without the shell of a vehicle surrounding them. In addition,
they are traveling at slower speeds than vehicular modes, and thus cannot react as
quickly to avoid dangerous situations as one with a motor vehicle could. On the
contrary, transit use is inherently a safer mode choice than personal vehicle travel.
Transit travel injury or fatality rate is about one-tenth the personal vehicle travel
%
14.0
%
15.2
%
57.2
%
59.3
28.8
%
25.5
%
%
0
20
%
%
40
60
%
80
%
100
%
Total U.S.
Southeastern U.S.
Bachelor's Degree or
Higher
High School to
Associate's Degree
Less than High School

rate, and transit oriented communities have about one-fifth of the per capita fatality
rates as automobile oriented communities (Litman, 2014). The safety increase with
transit is not only associated with the larger size of the vehicle which can absorb
more of the shock of an impact should an incident occur, but also with the
improvements of physical design of the infrastructure which often corresponds with
transit-oriented development (TOD).
2.2.3 Physical Design
TODs increase the safety for communities as a whole, most notably by giving
pedestrians and transit users “defensible spaces” and providing settings with fewer
hazards for non-motorists (TCRP Report 102, 2004). The change in physical design
of a network that implements TODs includes traffic-calming characteristics such as
speed humps, streetscapes with wide grassy medians and reduced width lanes to
further reduce the speed of vehicles. In addition other mixed-use land-use patterns
that are incorporated increase the overall safety of the network for all users.
Communities in the southern Sunbelt that were established and grew
dominantly in the post-war period were designed to accommodate automobile travel
and sprawling low density neighborhoods (Dangerous by Design, 2014). These
designs are not only more dangerous for vulnerable road users, but are also
inherently more dangerous for all modes of travel because of the tendencies to have
higher speed limits, wider lanes, and accommodate larger capacities. The arterial
focused designs are concentrated on the purpose of serving quick automobile travel.
Although the arterials are commonly populated with shopping centers, office parks,
and residential access, people or communities are too often the secondary

concerns, or non-concerns in the design process of the arterials (Dangerous by
Design, 2014).
The physical design however, is not only considering the safety of the
vulnerable road users, but also the effect of physical design on the fatalities of
vehicular road users. “Since 1979, the proportion of traffic fatalities involving the
collision with a fixed object on the roadside has fluctuated between nineteen and
twenty-three percent (Delgado, 2011).” In the southeastern region, it was
calculated by Wang (2006) that roadside hazards accounted for at least one death
in forty percent of all crashes in which a vehicle occupant was fatally injured. With a
ten percent higher share in the southeastern region, it is obvious that roadside
hazards play a role in the increase in fatality rates in the southeastern region.
2.2.4 Governmental Policies
The federal, state, and local laws and policies put in place have significant
impacts on the transportation system, with growing awareness on the emphasis on
quality of life and health, in addition to the efficient movement of people and goods
(CDC, 2010). The CDC has made several recommendations to increase the safety of
the transportation network. One recommendation includes providing the individual
states with incentives to implement and strengthen laws associated with: seat-belt
use, booster-seat use, helmet use for motorcyclists and bicyclists, impaired and
distracted driving, reducing speed limits, comprehensive graduated driver licensing,
improved roadway design, increased education on safe driving, bicycling, and
walking, and community designs that promote reduced speeds in neighborhoods.
The CDC also recommends increasing support for new technologies to improve the

safety of motor vehicles and enable vehicles to withstand crashes with lower risk of
injury to the occupants and non-occupants, and also new technologies to prevent
alcohol impaired driving (CDC, 2010).
2.2.4.1 Seat Belt Policies
Wearing a seat belt reduces the likelihood of occupant death by roughly sixty
percent, when involved in a motor vehicle accident (Levitt and Porter, 1999). When
states pass laws to require the use of front-seat occupants to wear seat belts, the
average seat belt usage rates increase about seventeen percent (Cohen and Einav,
2001). Table 3 displays the southeastern states and their primary seatbelt policies
in addition to some national comparisons. Some states currently have secondary
seat belt laws, which require the driver to be pulled over for an unrelated offense,
and do not allow law enforcement to stop a vehicle for the sole purpose of not
wearing a seat belt. In other states, seat belt laws are primary offenses, meaning
law enforcement can stop a vehicle for the sole purpose of not wearing a seat belt.
It was estimated that if all states which had secondary seatbelt enforcement laws in
2001 changed their laws to primary, the national seat belt usage rate would have
increased from 68% to 77% and in turn would have saved approximately 500 lives
per year (Cohen and Einav, 2001). When comparing seat belt usage between states
with primary seat belt laws and states with secondary or without seatbelt laws, in
2013 the share of seat belt usage varied by 11% (Traffic Safety Facts, 2014). The
trends from 1995 to 2013 show a reduction of Daytime percent unrestrained personal
vehicle occupant fatalities associated with an increase in overall safety belt usage
(Traffic Safety Facts, 2014). Booster seat laws have similar safety influences as seat
belt laws. Booster seat laws were associated with a 17% reduction in the per capita

rate of children who sustained fatal or incapacitating injuries from motor vehicle
accidents (Eichelberger, A.H., Chouinard, A.O., Jermakain, J.S., 2012).
Table 3 Primary Seat Belt Policies
Alabama
Front Seat only
Florida
Front seat and minors in rear seats
Georgia
Front seat and minors in rear seats
Kentucky
All
Mississippi
Front Seat only
North Carolina
Front (secondary for rear seat)
South Carolina
All
Tennessee
Front Seat only
Nationally
33 states have primary front seat laws (17 primary all seats)
Data Source: GHSA
2.2.4.2 Helmet Policies
Motorcycle helmet laws vary among the states, with some states having
universal helmet laws, some states having partial helmet laws, and a few states
having no helmet laws at all as of February 2015. A universal helmet law is
inclusive of all motorcycle riders regardless of age, experience, or insurance
coverage. Many states also extend the helmet laws to cover riders of low-powered
cycles which are not classified as motorcycles, such as mopeds and scooters, while
some states specify the extension to low-powered cycles with specific minimum
engine displacement, braking, and/or top speed specifications. A partial helmet law
is generally age dependent, with some states having additional dependent criteria
as well. As of February 2015, There are currently three states in the U.S. which
have no helmet laws at all; Illinois, Iowa, and New Hampshire. Currently 19 states

and the District of Columbia have universal helmet laws, and 28 states have partial
helmet laws. The majority of the states in the southeastern region of the U.S. have
universal helmet laws with the exception of Florida and South Carolina. The partial
helmet laws in Florida are inclusive of all riders under the age of 21 without
exception, and riders over the age of 21 who do not carry a minimum of $10,000 in
medical insurance. From 1967 to 2000 all motorcycle riders in Florida were required
to wear helmets; however the law was changed to a partial law in July of 2000. In
South Carolina, all riders under the age of 21 are required to wear a helmet, but
once the rider reaches the age of 21, there are no applicable helmet laws. From
1967 to 1980 there was a universal helmet law in effect in South Carolina, at which
time the law was reduced to a partial law covering only riders under the age of 21
(Motorcycles, 2015) . Motorcycles require important consideration when trying to
reduce overall traffic fatality rates because motorcyclists account for a
disproportionate share of traffic fatalities. In 2011 motorcyclists accounted for 14
percent of all traffic fatalities while only accounting for less than one percent of all
vehicle miles of travel (Traffic Safety Facts, 2013). Helmet laws are closely
correlated with helmet use and with motorcycle fatalities. In states where a
universal helmet law was repealed, the average helmet use decreased 41% and the
total number of motorcycle fatalities increased 38% (Use of Motorcycle Helmets:
Universal Helmet Laws, 2014). On the contrary, states that changed from partial or
no helmet laws to universal helmet laws experienced an increase in helmet use of
56% and a decrease in motorcycle fatalities of 37% (Use of Motorcycle Helmets:
Universal Helmet Laws, 2014).

2.2.4.3 Distracted Driving Policies
While the term distracted driving is defined by the National Highway Traffic
Safety Administration (NHTSA) as inattention that occurs when a driver diverts their
attention away from the task of driving to focus on another activity (Driver
Distraction Program, 2010), distracted driving laws generally only pertain to the use
of electronic devices (Distracted Driving Laws, 2015). Alarmingly, no state in the
U.S. bans all cell phone use while driving, and only twenty states prohibit cell phone
use for school bus drivers, and thirty-eight states ban cell phone use for novice
drivers. The definition of novice driver varies by state and is usually determined by
the level of licensure and/or by the driver’s age. Currently forty-four states have
texting while driving bans in place, and in the southeastern region, that is inclusive
of all states except Mississippi, which only prohibits texting while driving for school
bus drivers and drivers with learners’ permits. Distracted driving accounts for
approximately ten percent of all fatal crashes in the U.S. and nearly one in every
five (17%) injury crashes (Traffic Safety Facts, 2013). It has been demonstrated
that high visibility of law enforcement is an effective way of reducing cellphone/text
message use while driving in certain situations. This measure is reliant on increased
law enforcement presence in addition to increased media coverage about the
increased enforcement, which in turn increases the perceived risk of being caught
violating the law. This measure is of course, only effective where laws are in place
to deter drivers from distractions. While this measure has only been implemented in
a few states, Hartford, Connecticut saw a hand-held cell phone use decrease of
57% (Countermeasures That Work, 2013).

2.2.4.4 Drunk Driving Policies
Driving while drunk or intoxicated is a crime in all states in the U.S.; however
the definition of the legal limit of blood alcohol concentration (BAC) varies greatly
across states. In all U.S. states the minimum BAC to receive a penalty for driving
under the influence (DUI) is 0.08. Other states have additional penalties for
excessive BAC limits which vary from 0.10 in Rhode Island to 0.20 in Florida and
Tennessee (GHSA, 2015). Many countermeasures to deter drivers from driving
under the influence have been proven to be effective such as; revocation or
suspension of license for refusal to submit to a BAC test, publicized sobriety
checkpoints, saturation patrol of areas prone to DUI’s during specific times when
DUI’s are at the highest, generally associated with the closing of the local alcoholic
establishments (Countermeasures That Work, 2013). Mothers against Drunk Driving
(MADD) was established in 1980 when a mother lost her daughter in an accident
caused by a drunk driver, and the goal of MADD was to make the drunk driving laws
stricter (Ronis, 2014).The effectiveness of strengthening DUI laws was reflected in
the reduction of fatalities associated with drunk drivers. Between 1982 and 2005
the share of drivers in fatal crashes with BAC of 0.08 or higher decreased from 35
percent to just 20 percent (Statistical Analysis of Alcohol-Related Driving
Trends, 2008).
2.2.4.5 Speed Policies
Speed is greatly associated with the severity of a collision, especially when a
pedestrian is involved. Figure 4 shows how the percentage of pedestrian fatalities
increases with speed increments of just 10 miles per hour (mph). “Studies suggest
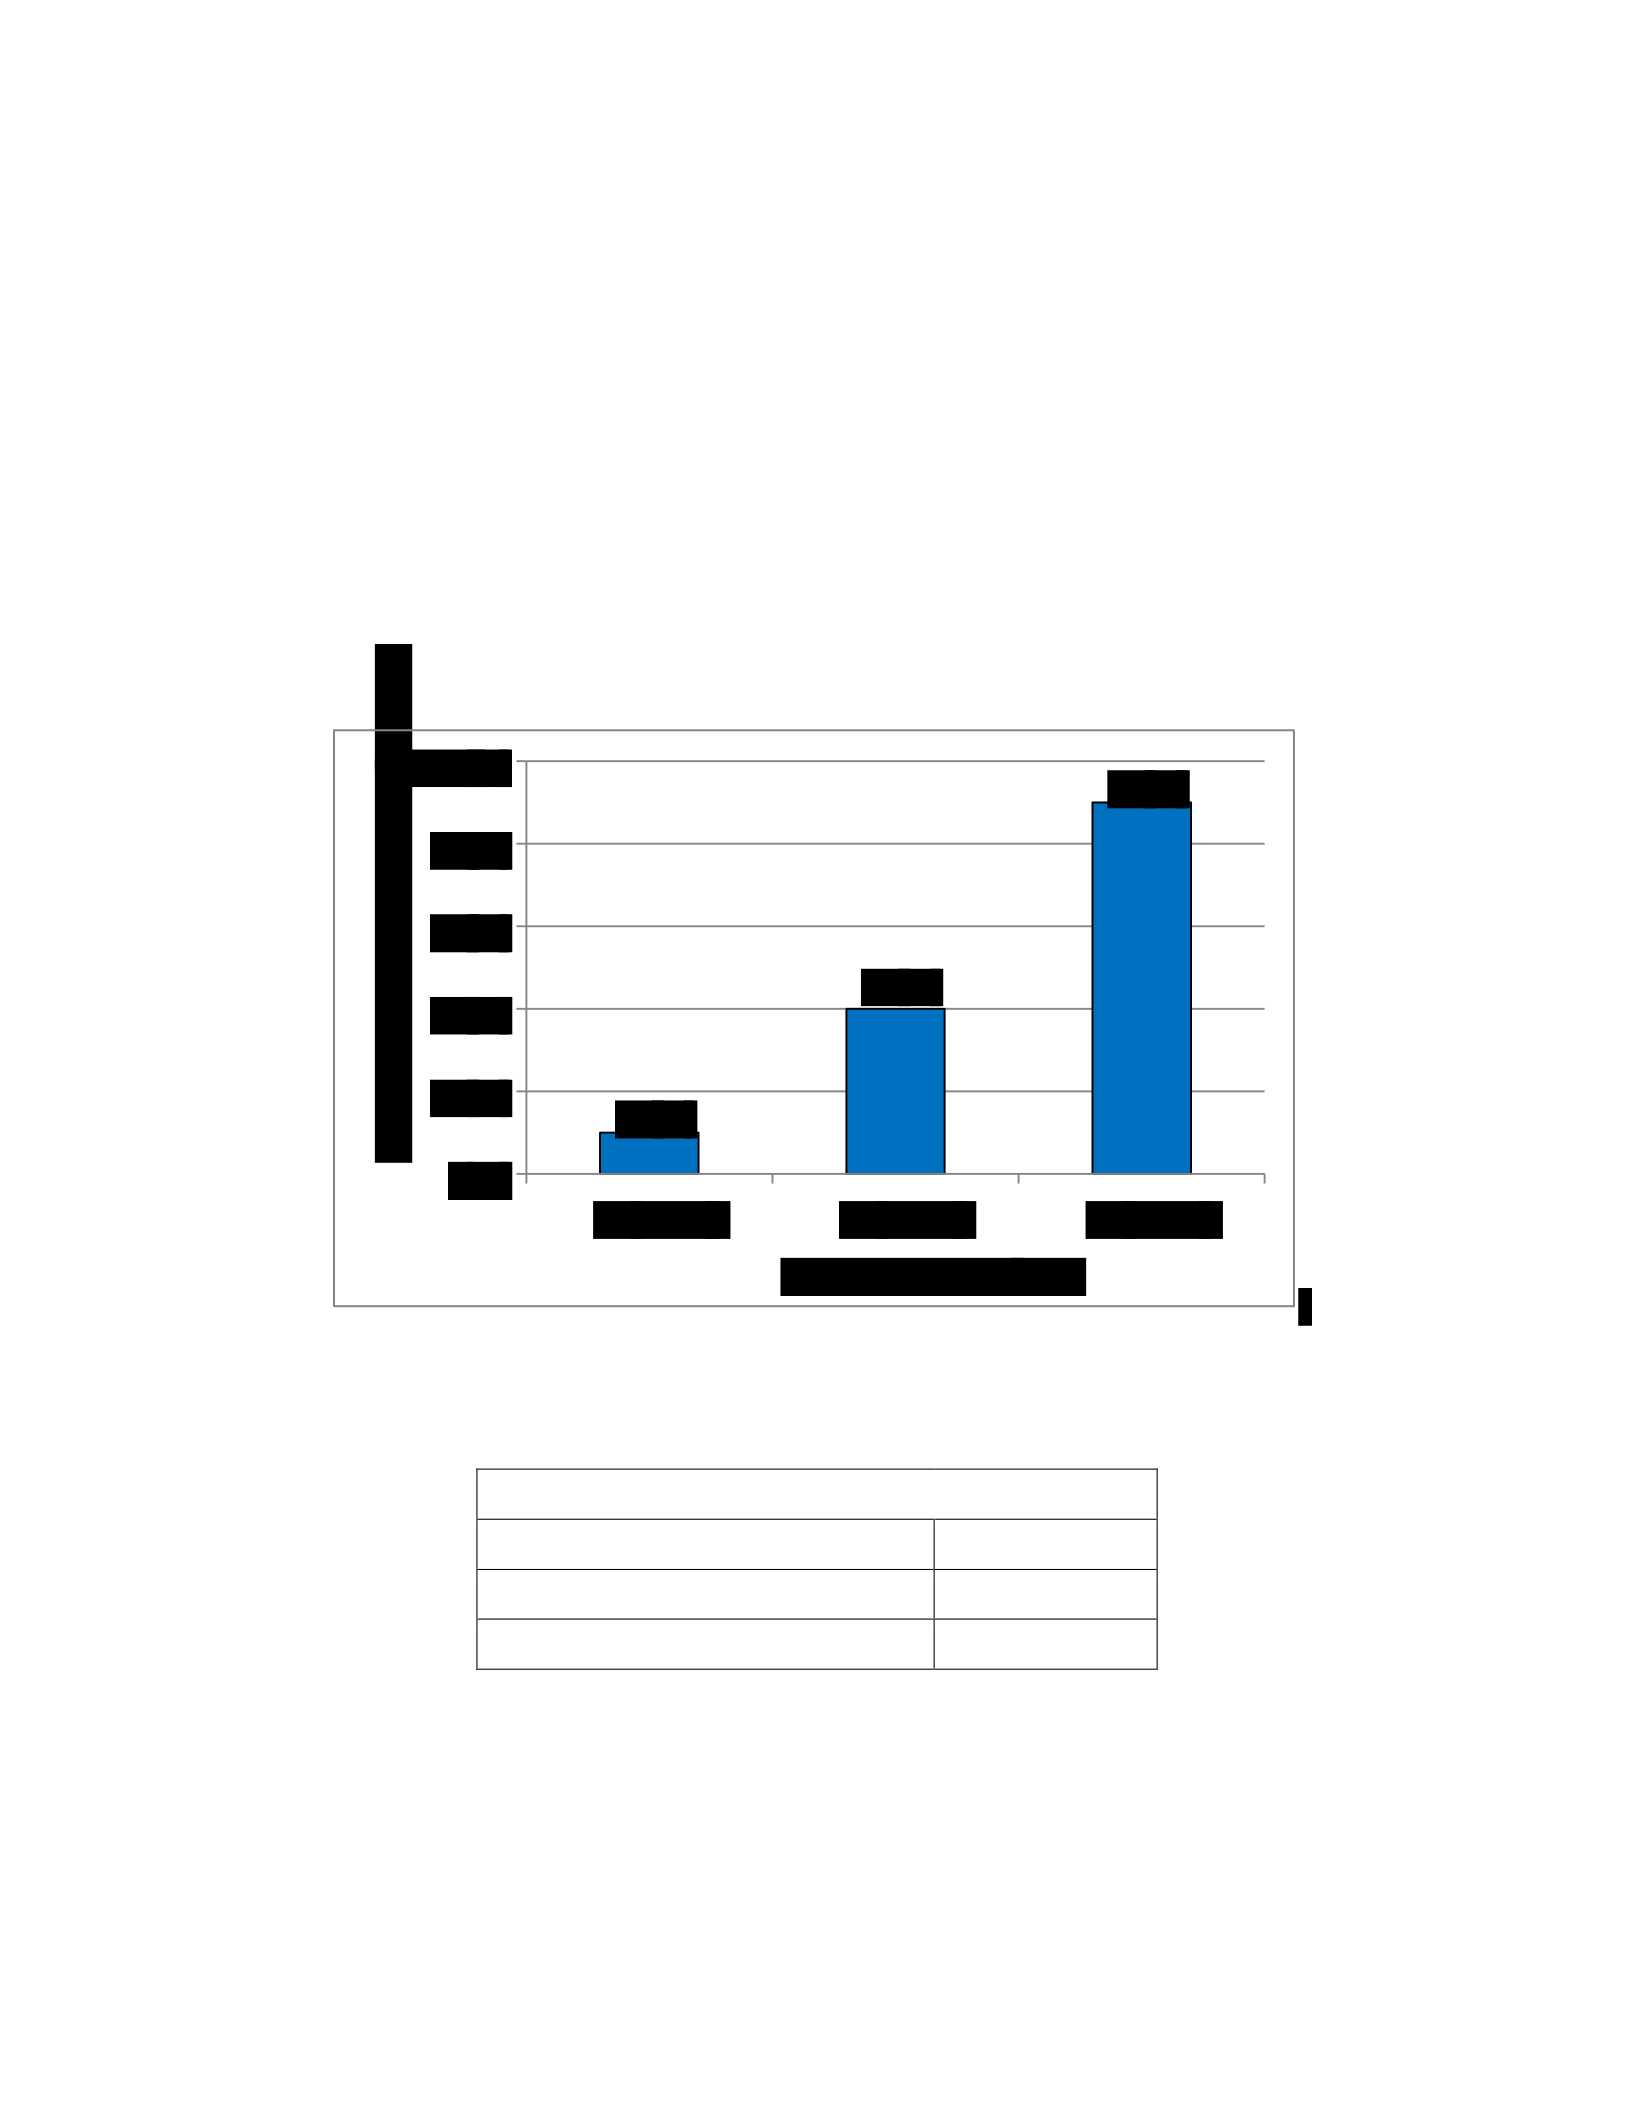
that a fatal pedestrian accident is 6 times less likely to happen if the vehicle speed
is 23 mph as opposed to 28 mph” (Photo Enforcement Program – Historical
Perspective, 2006). Photo enforcement programs installed to enforce speed limits in
school zones have shown to be effective in reducing the number and severity of
speeding drivers, thus making the network safer for all users (Photo Enforcement
Program – Historical Perspective, 2006). The southeastern region, highest and
lowest top speeds are shown in Table 4.
Figure 4 Pedestrian Fatality Share by Vehicle Speed. Amended from: Photo
Enforcement Program – Historical Perspective, 2006. City of Renton, WA.
Table 4 Top Speeds
Top Speed by St
ate
All SE States
70
Lowest (Alaska)
55
Highest (Texas)
85
Data Source: motorists.org
%
10
40
%
90
%
0
%
%
20
40
%
60
%
%
80
100
%
20
mph
30
mph
40
mph
Vehicle Speed

2.2.5 Environmental Variations
There are several factors to be considered when trying to distinguish the
reasoning behind the higher than average fatality rates in the southeastern region,
and one factor which cannot be over looked is the environmental differences. The
southeastern region of the U.S. has much milder winters than the rest of the
nation. If we compare the average high temperatures in the historically coldest
months of the year, December through February, in Tampa, Florida the average high
temperature is in the 70’s, in Montgomery, Alabama the average high temperature
is in the 60’s, and in Memphis, Tennessee the average high temperature is in the
50’s. However when those average high temperatures are compared to some states
in the northern parts of the U.S. a much colder trend is apparent. The average high
temperature in those same months in St. Paul, Minnesota is in the 20’s, which is
similar to Bismarck, North Dakota. And the states in the Northeastern region of the
state average highs are in the 30’s and low 40’s (U.S. Climate Data, 2015). In
addition to the milder temperatures of the winter, the higher temperatures in the
summer are often reasoning to wait until the sun goes down to participate in
outdoor activities in the warmer months. For instance, one may choose to go before
sunrise or wait until sunset to go for a jog outside because those are the times
when the temperatures are milder during the summer months.
This overrepresentation of pedestrians and bicyclists in the dark may be an
explanatory factor in the increased number of pedestrian fatalities in the
southeastern region.
In general, one state in the southeastern region stands out from the rest in
visitor attractiveness, Florida, also known as the “Sunshine State”. Orlando is the

leader of all cities in the U.S. at attracting visitors, with over 48 million attracted in
2009 (Forbes, 2010). With the warm weather, tons of amusement parks, over
thirteen hundred miles of coastline accompanied by breathtaking beaches and the
largest cruise market in the world, Florida is major attractor of visitors, both
domestically and internationally (Census, 2010). In 2013 Florida received nearly 94
million visitors (VisitFlorida, 2015). With this amount of tourists visiting the state
each year, there is a disproportionate share of unfamiliar drivers on the roadway
network in the Sunshine State. It has been found that the volume of tourists or
visitors who are unfamiliar drivers are proportionate to the number of traffic
fatalities in the region, meaning as the number of unfamiliar drivers increases on
the roadway network, so too does the number of traffic fatalities
(Somasundaraswaran, 2010). The combination of outdoor inviting weather, and
increased share of unfamiliar drivers on the roadway play a significant role in the
increased number of pedestrian and bicycle fatalities in the state of Florida
(Dangerous by Design, 2014). This same reasoning could also be extended to
motorcycle fatality rates in the state, with weather conditions which make it inviting
to ride a motorcycle year round, and a greater proportion of unfamiliar drivers on
the network, it is a recipe for increased fatalities (Reyes, 2013).
2.3 Risk-Taking Characteristics
Risk-taking characteristics are descriptive of behavior which can be perceived
as risk-taking behavior. For this thesis, the adopted definition of risk-taking behavior
is defined as “the tendency to engage in behaviors that have the potential to be
harmful or dangerous, yet at the same time provide the opportunity for some kind

of outcome that can be perceived as positive(Tull, 2014).” Risk-taking
characteristics may not only be tied to an individual’s specific driving behavior, but
also to the propensity to procrastinate on general upkeep of the vehicle, such as
changing tires, brake pads, and oil on a routine basis. As the upkeep of a vehicle is
neglected, the chances of vehicle failure of some kind increase, and the risk of
incident also increases. In this thesis the types of risk-taking characteristics will be
limited to the following; credit score, smoking and tobacco use, alcohol use, drug
use, mental health, obesity, general health, and educational attainment. A credit
score is a risk-taking characteristic because it gives an idea of the financial
responsibility of the credit holder, and thus a lower credit score is often tied to an
individual who takes more financial risks than an individual with a higher credit
score. Tobacco use, alcohol, and drug use are all associated with adverse health
characteristics and each present different levels of risk users are exposing
themselves to. Mental health, obesity, and overall general health may not be as
straight forward as the previous risk taking characteristics; however they are
associated with general risk. For example, someone who suffers from some form of
mental instability may be more likely to engage in risky behavior, which they may
not be able to control, and while the mental disability is not a risk they chose, it is
still a contributing factor to their life (Guiang, 2014). Finally education levels are
generally correlated with income levels, specifically of the family. It has been shown
that youth from low income families are less likely to graduate from high school, get
a degree, and are more likely to engage in risky behaviors (Kent, 2009).

2.3.1 Credit Score
Beginning with perhaps the most controversial of all risk taking or cultural
behavior traits, credit score is already used in 47 states within the U.S. as a factor
to predict the consumer’s likelihood and amount of insurance losses, with the
exception of Massachusetts, Hawaii, and California. To clarify credit-based scoring is
not the sole factor in determining the amount of an individual’s automobile
premium, it is just one of several factors used in the calculation of risk, which varies
by insurance company, explaining why the same person may pay a much different
premium for the same automobile depending on which insurance agency their
automobile insurance is issued through. According to the National Association of
Insurance Commissioners (NAIC) credit-based scores were introduced in the 1990’s
and 95% of auto insurers that are able to use credit-based insurance scores do so,
citing that research shows a correlation between credit scores and insurance losses.
A credit-based insurance score is not exactly the same as a general credit score, as
it only uses specific aspects of an individual’s credit score to rate them, such as;
payment history, outstanding debt, credit history length, pursuit of new credit, and
credit mix (NAIC, 2012). The Insurance Information Institute (III) states, “Studies
have shown a 99 percent correlation between insurance scores and loss ratio,”
meaning individuals with low credit-based insurance scores, account for a higher
share of the claim dollars paid. In July of 2007 the Federal Trade Commission (FTC)
released a report to Congress on the impacts of credit based scores on consumer
automobile insurance, which determined that score based predictors were much
more accurate than using race and ethnicity. The report also states while there is no
definitive reasoning as to why the low credit scores, on average, lead to higher

amounts and rates of claims, the report did give some reasoning as to why strong
credit history likely leads to reduced claims. The FTC report states:
“A strong credit history, however, might indicate that a consumer has taken
care in managing his or her financial affairs by avoiding loans that might be
difficult to repay, avoiding high balances on credit cards, making sure that
bills are not misplaced and are paid on time, etc. A consumer who is prudent
in financial matters may also be cautious in other matters related to
insurance, such as being more likely to put time, effort, and money into
things like car and home maintenance, cautious driving habits, etc. An
overall inclination to be prudent may lead a consumer both to have a strong
credit history and file fewer insurance claims.”
It should be noted that this credit-based insurance scoring reasoning is based on an
average, and is not completely explanatory for each individual circumstance;
however it is the best way currently available to predict losses, or more precisely,
loss ratios. It should also be noted through this same FTC study, that 59 percent of
consumers are predicted to have lower premiums when credit-based scoring is used
instead of previous methods of calculating premiums without using credit as a
factor.
2.3.2 Smoking and Tobacco Use
Other risk-taking behavior includes one’s choice to use tobacco, alcohol, or
illicit drugs. These decisions can be greatly tied to cultural effects, as the probability
of an individual to choose to partake in these specific behaviors is often much
greater when the individual was exposed to these behaviors throughout their

childhood. The Center for Disease Control and Prevention (CDC) reports that the
probability of use of alcohol and other drugs is correlated to the probability of
tobacco use. In addition, 99 percent of tobacco users report trying tobacco before
their 26th birthday, indicating that it is extremely rare for an adult who never tried
tobacco to pick up the habit after their 25th birthday. This is also indicates that
teens and young adults are generally more impressionable, have less understanding
or care of the consequences related to their behavioral choices, and thus more
likely to take risks in general. Many teens who are aware of the consequences
associated with smoking, drug use, or alcohol use think that the consequences do
not apply to them, which can also be mirrored in their choice to behave in a risky
manner while driving, because again, they think that they are the exception; that
crashes happen to everyone else, but not to them. Social groups such as peers and
family members have a great influence on the probability of youth to use tobacco,
because they tend to see it as acceptable or normal. Other influences demonstrated
to affect tobacco use include low socioeconomic status, low education levels, low
self-esteem, and exposure to tobacco advertising. Smoking and other use of
tobacco is categorized as risk-taking behavior because it is known to have adverse
effects on health ranging from bad breath and foul-smelling clothes to diseases
such as cancer and even death. The CDC reports that smoking harms nearly every
organ of the body and is tied to nearly one in every five deaths in the U.S.
Individuals who are willing to take the risks associated with the use of tobacco are
also likely to take risks in other aspects of their life, including the way they drive. It
is arguable that if an individual is willing to smoke, they have less regard for the

human life, and thus are more likely to drive erratically, aggressively, while
distracted, or in other circumstances that would otherwise be considered risky.
2.3.3 Drug Use
Drug use, while highly correlated with tobacco use. The U.S. Federal
Department of Health and Human Services has an agency called SAMHSA, which
stands for Substance Abuse and Mental Health Services Administration, whose
mission is to “reduce the impact of substance abuse and mental illness on America’s
communities.” Drug use is known to have adverse health effects on the user, and
thus when an individual chooses to use any drug, they are in turn willing to put
their body at risk. This general idea has inspired several studies, many of which
compare adolescent substance use with risky sexual behavior. It has been found
that substance using adolescent females had higher rates of sexually transmitted
diseases, and more pregnancies than non-abusing adolescent females (Tapert, et.
Al., 2001). To focus back to the risk of interest of this thesis, driving and fatal crash
risk, it has been found that the “use of drugs while driving tends to have a larger
effect on the risk of fatal and serious injury accidents than on the risk of less
serious accidents” (Rune, 2013). One aspect of risk-taking is sensation seeking, or
trying to attain a feeling of euphoria or excitement. Sensation seeking as a
construct predicts alcohol use, smoking, sexual behavior, substance use, and
driving under the influence (Ames, et al., 2002). Several studies have associated
sensation seeking with not only substance use/abuse, specifically marijuana, such
as Satinder and Black (1984), but also associated sensation seeking with erratic
and aggressive driving such as Jonah (1997). With current ever-changing laws

associated with marijuana use at the present time, it is important to note that “the
more prevalent and socially acceptable a drug is in a particular population, the less
likely it is to find a relationship between the use of that drug and sensation-seeking
orientation (Satinder and Black, 1984).” This is particularly important when
referring to marijuana use in the U.S., because as of 2015, twenty-three states and
the District of Columbia have legalized some type of marijuana use, whether
medical or recreational (governing.com, 2015).
2.3.4 Mental Health
Adults with symptoms of depression, just one type of mental disability, were
significantly more likely to engage in certain risk behaviors than persons without
depression (Mental Health in the United States, 2005). A study by Prochaska et al.
studied 693 people with serious mental illness for the number of risk-taking
behaviors they participated in. The average number of risk-taking behaviors the
sample of serious mentally ill participated in was 5.2 with 100 percent using
tobacco, 68 percent eating high fat diets, 46 percent using marijuana, and 26
percent binge drinking. The seriously mentally ill population is more vulnerable and
thus more impressionable into making risky behavior choices such as smoking
(Prochaska, et al., 2014) Chwastiak et al. conducted a report on veterans with
serious mental illness and found there is an increased risk for mentally ill patients
to have multiple health risk behaviors. The NHTSA held a symposium in 1999 where
the Executive Director of the Institute for Mental Health Initiatives, Mr. Michael
Benjamin, addressed the topic of aggressive driving. Mr. Benjamin mentioned that
aggressive driving is a characteristic of high-risk-behavior individuals often with
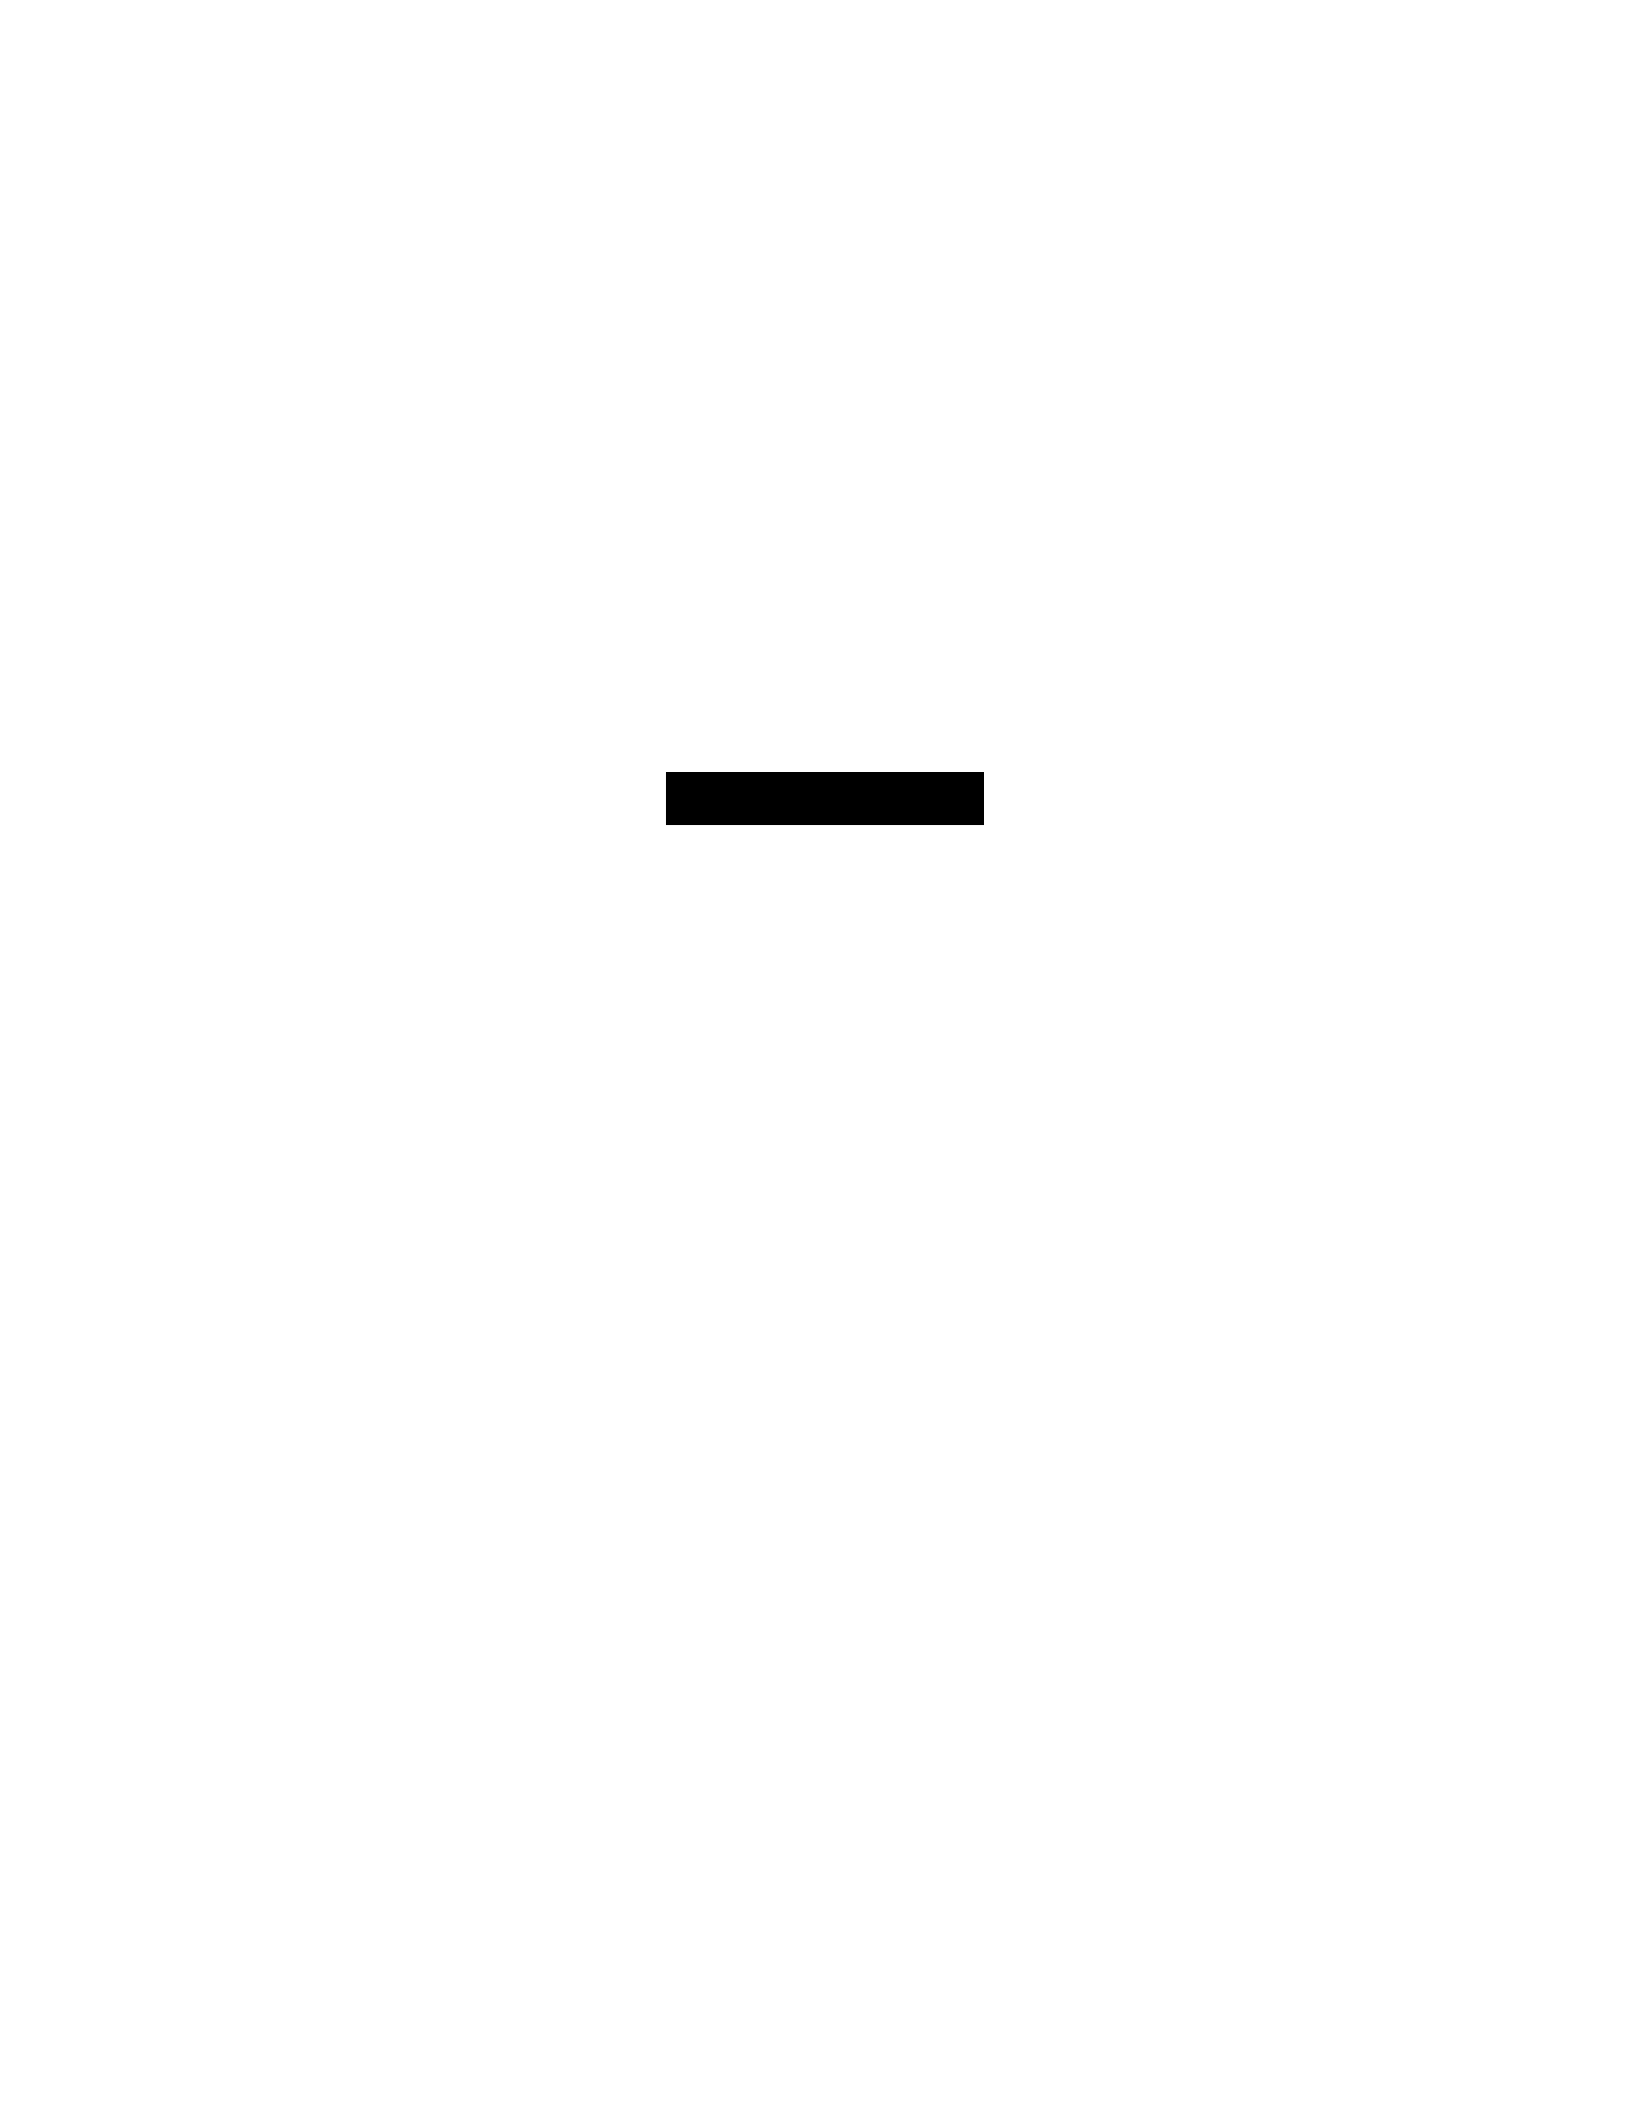
uncontrolled anger and violence, requesting that aggressive driving improvement
strategies be incorporated into driving education and anger management classes
(NHTSA, 1999).
2.3.5 Obesity
Obesity is defined as having an excessive amount of body fat, measured as a
body mass index (BMI) of 30.0 or higher, calculation is shown in Equation 1 (Mayo
Clinic, 2014).
Equation 1
According to the researchers at the Mayo Clinic, obesity is usually a result of a
combination of genetics, lifestyle, inactivity and unhealthy dieting, although even
when ramped within a family, diet and exercise can mitigate and control onset of
obesity. Obesity is often a result of choices made by an individual, whether
conscious or subconscious, and is related to several other quality-of-life altering
characteristics such as depression, shame, social isolation, lower work achievement,
etc. (Mayo Clinic, 2014). The mentioned mental characteristics are known to affect
ones increased propensity to engage in risky behavior, thus obesity can also be
associated with an individual’s increased propensity to behave in a risky manner.
In 2003, Arbabi S, et al. wrote “The Cushion Effect” in which they stated
that, “In motor vehicle accidents, obese individuals are less likely than
normalweight individuals to suffer abdominal and pelvic injuries.” However a
nonlinear relationship was discovered in the study, and overweight people tended to
have lower fatality risk than normal weight and obese patients, with an implication
that the cushion effect is optimal when the patient has not yet reached the level of

obesity, where other factors affect the health of the individual (Arbabi, 2003). Since
that publication another study (Cramer C. et al.) indicates, “More protective soft
tissue leads to changing absorption and distribution of energy, thereby serving as
protection for abdominal organs.” This could be a possible indication that obesity,
while leading to more risk-taking behavior may not have as large effect as initially
considered in overall average vehicular fatality rates by geography.
2.3.6 General Health
General overall health, as assessed in the Behavioral Risk Factor Surveillance
System (BRFSS) is self-determined, however is surveyed along with several other
behavioral health questions, thus is assumed to be relatively related to chronic
diseases, healthy behaviors, and access to preventative health-care services. The
top five causes of death in the U.S. according to the CDC are heart disease, cancer,
lower respiratory diseases, accidents, and stroke; at least four of which are effected
by risk-taking health decisions made by an individual. Accidents’, meaning any
unintentional injury, is the only one that is not necessarily effected by health related
risk-taking behavior (CDC, 2015). The most common known causes of heart
disease, cancer, respiratory diseases and stroke are unhealthy diet, lack of
exercise, being overweight, and smoking (Mayo Clinic, 2015), all of which are due
to risk-taking choices made by an individual, with some added risk from air
pollution, allergens, and occupational agents (WHO, nd).

2.3.7 Educational Attainment
Obtaining an education is not a risk taking behavior, but rather the lack of
educational attainment is a risk taking behavior. Referring back to the established
definition of risk taking presented earlier in the introduction of this thesis, an action
that can be dangerous or harmful with the perception of some type of positive
outcome; dropping out of school may be viewed as a positive outcome by a young
individual who experiences less responsibility and more free time, however their
future success can be harmed by the action of dropping out of school. “People with
more education are likely to live longer, to experience better health outcomes, and
to practice health-promoting behaviors such as exercising regularly, refraining from
smoking, and obtaining timely healthcare check-ups and screenings (Education
Matters for Health, 2009).” Educational attainment and poverty are interrelated,
with the Federal Educational Testing Service (ETS) reporting that adults who grew
up in poverty are likely to achieve a lower level of educational attainment, have
lower earnings when they enter the work force, pay less in taxes, and “exhibit
negative behaviors and health outcomes that add a burden to the nation’s
economy” (ETS, 2013). In other words, the less education a person completes the
more likely that person is to act in a risky manner, including breaking laws and
endangering their health. Education has also been linked to sense of control,
indicating that as an individual’s education levels increase they gain a greater
perception of how their actions influence their circumstances (Education Matters for
Health, 2009). Thus, the individual will be less likely to act in a risky manner, given
a better understanding of the possible outcomes associated with the risky behavior.

As education levels increase, the healthy behavior levels such as healthy diet,
exercise, and lack of smoking, increase, and life expectancy increases (Maralani,
2014).

CHAPTER 3:
DATA COLLECTION AND METHODOLOGY
The following sections of chapter three review the data collected from each
source, along with the methodologies used in the collection of each set of data. The
large range of data sources resulted in varying methodologies. The final sections of
chapter three describe the methodology used in the data analysis performed.
3.1 Fatality Rates
Fatality rates can be defined as fatalities per one hundred million vehicle
miles of travel (VMT), to account for exposure. Fatality rates can also be defined as
fatalities per population, to give an overall risk per person. In a previously
mentioned report, Dangerous by Design, mode specific fatality rates are calculated
by approximate exposure. For example, pedestrian volumes are not adequately
reported, so often an estimation of propensity to walk as a mode choice is
estimated along with historical pedestrian fatalities to calculate a pedestrian fatality
rate. To account for regression to mean, the fatality rates used in this thesis are
always an average of three years of data. According to De Pauw, et al. regression to
mean is referring to the phenomena that high crash frequency periods are often
followed by low crash frequency periods which occurs due to the randomness

associated with vehicular crashes. Regression to mean uses multiple years of data
to account for fluctuations which over time generally represent a mean value.
Without using multiple years of data to account for regression to mean, the data
may be under-representative or over-representative of the actual fatality rates
(DePauw, et al., 2014.) The following sections describe the data which was collected
and the methodology of each source of data that was used in the determination of
fatality rates.
3.1.1 Fatality Analysis Reporting System
The Fatality Analysis Reporting System (FARS) was the data source used to
gather and examine all of the fatality rates, and all of the specific characteristics of
the fatalities. The FARS (2013) reports fatality information and characteristics in
eighteen data files, three of which were used to evaluate the given data, the crash
level file, the vehicle level file and the person level file. The levels of data are shown
in Table 5.
Table 5 Levels of Data in FARS
Name
Variables Includes
Crash
crash level
Vehicle
vehicle level
Person
individual specific
Parkwork
parked and working vehicles
cevent
sequence of all qualifying events, e.g. crossed center line
vevent
sequence of events for each vehicle
vsoe
sequence of events for each in-transport vehicle
distract
driver distractions
factor
vehicle circumstances
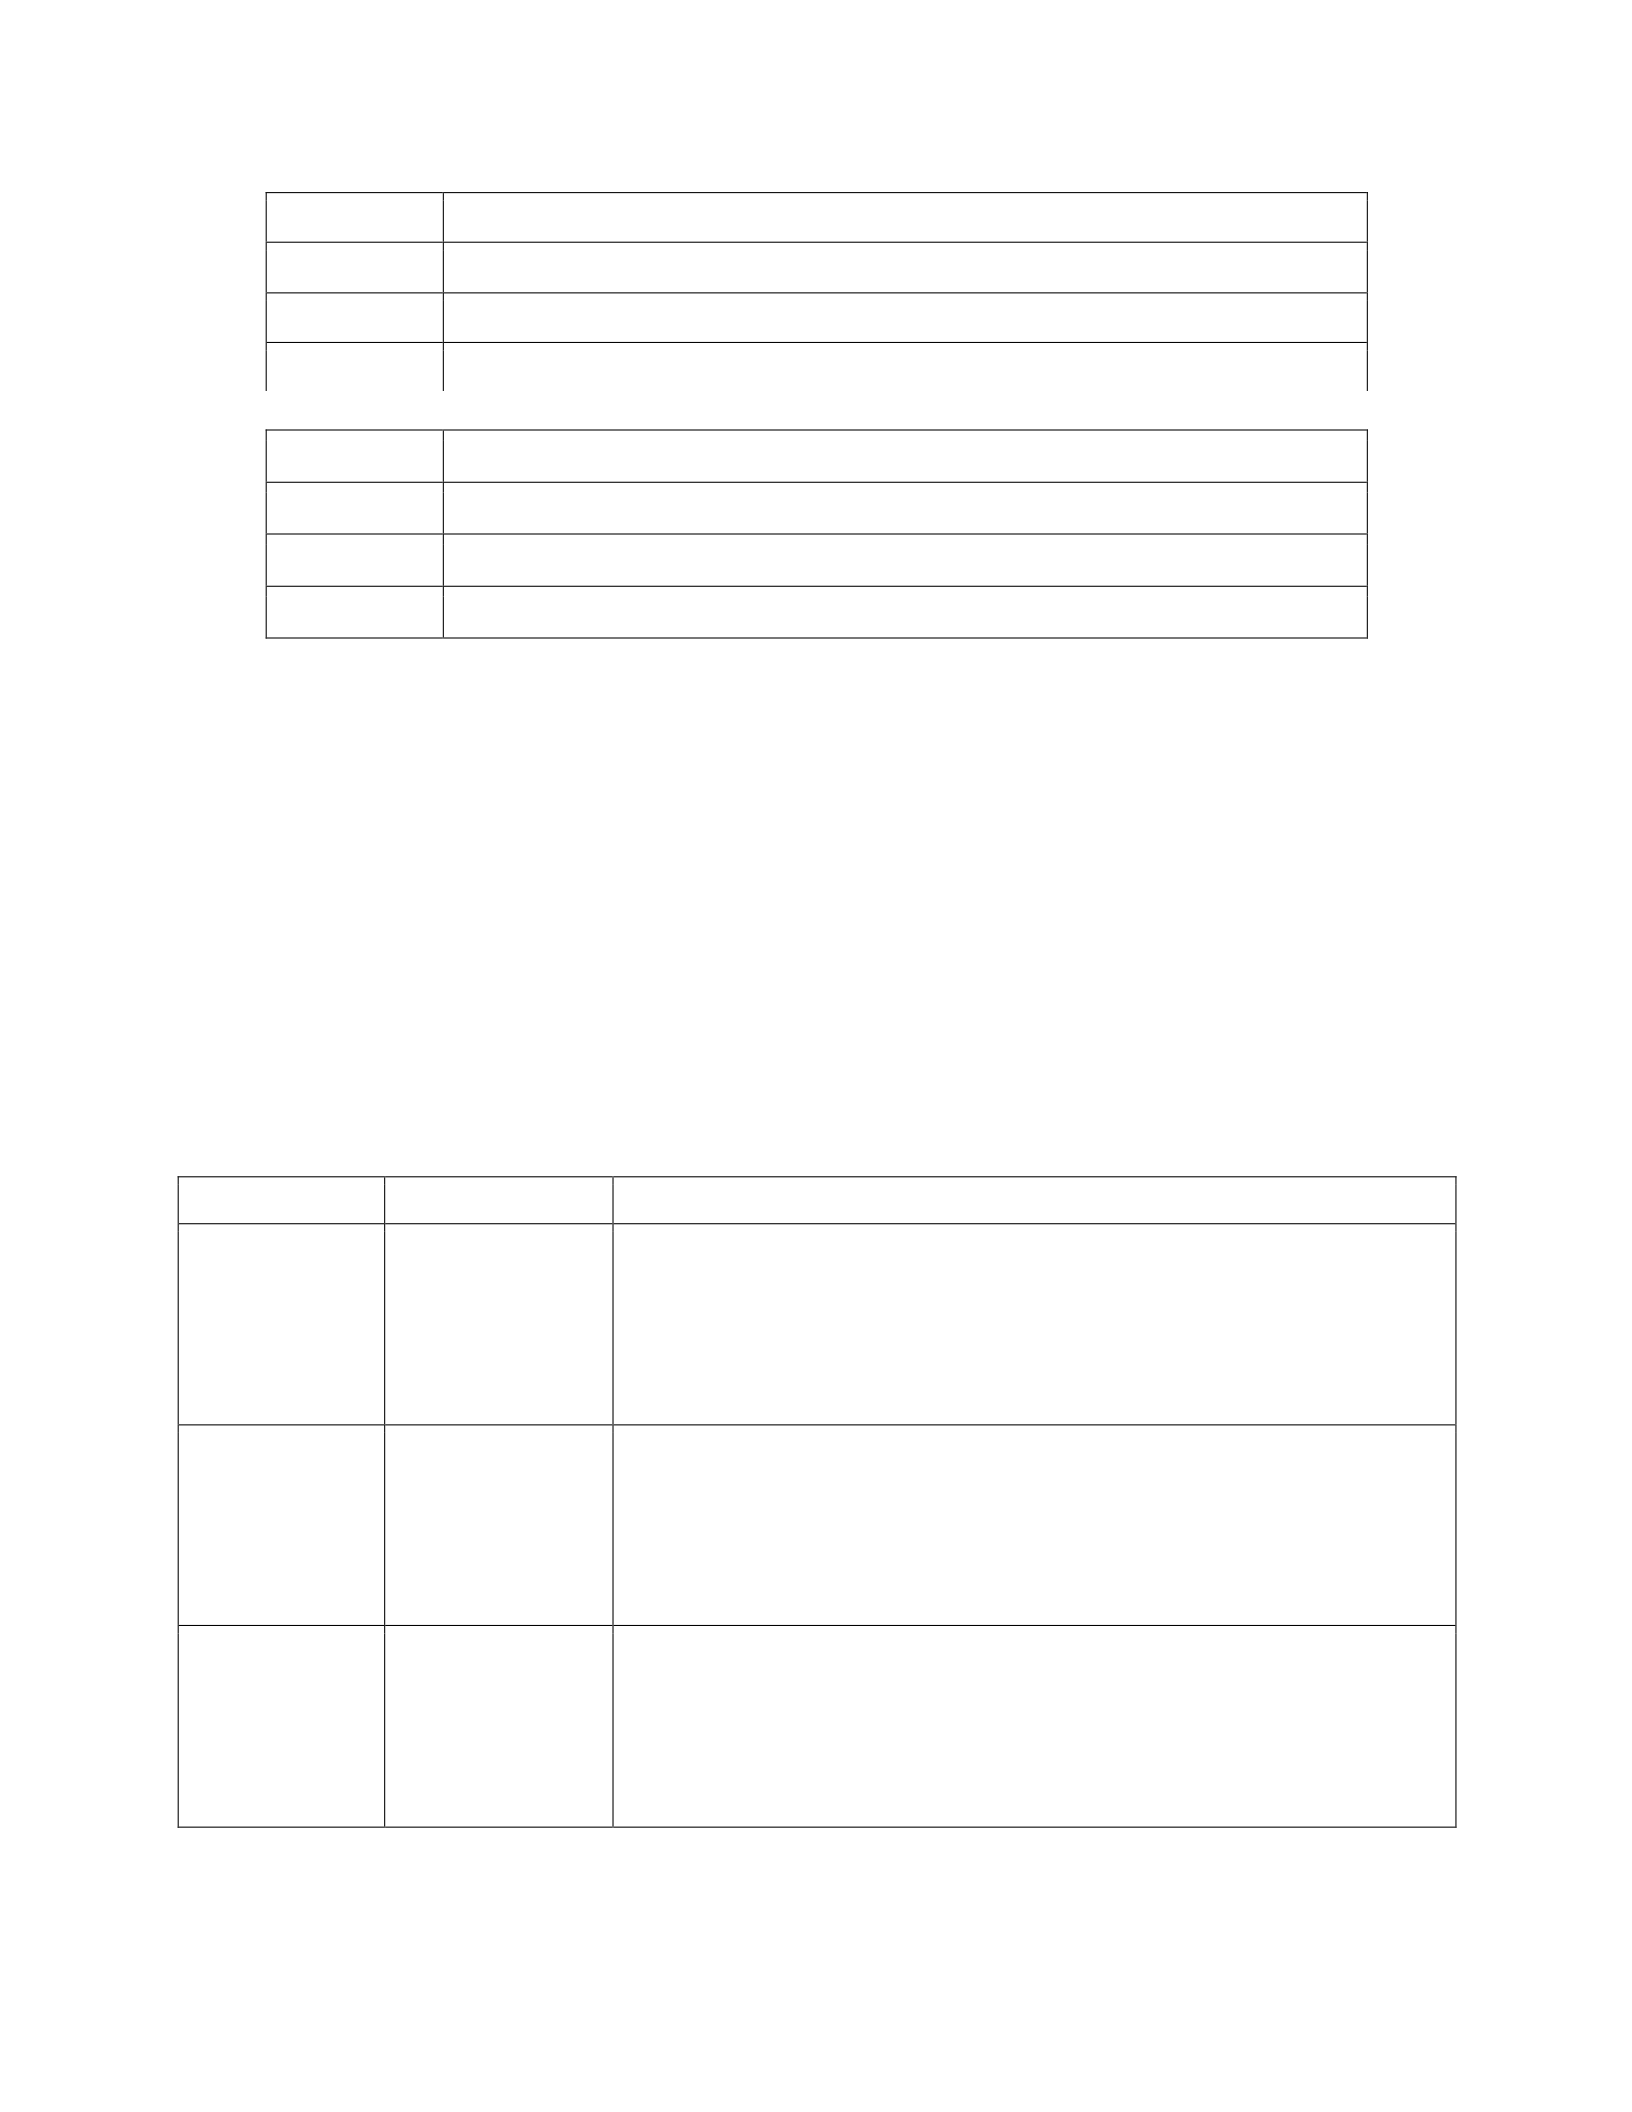
drimpair
physical impairment of driver od motor vehicle
nmimpair
physical impairment of non-motorist, e.g. pedestrian
maneuver
actions taken by driver to avoid something or someone
nmprior
what non-motorists are doing prior to crash
Table 5 Continued
safetyeq
safety equipment used by non-motorists
violatn
violations charged to drivers
vision
circumstances which may have obscured the driver’s vision
damage
all areas of vehicle damaged in the collision
Data Source: Fatality Analysis Reporting System, 2013
There are several characteristics which are present in several levels of reported data
files used such as; the state the crash occurred in, the date, time, and location of
the crash, and the roadway function where the crash occurred, as shown in Table
6.
Table 6 Data Level Inclusivity
Data Level
Entries
Includes
Crash
1 per crash
number of: vehicles involved, occupants, fatalities and
weather, lighting conditions, manner of collision, first
harmful event, related factors, work zone details,
school bus, rail crossing, time of EMS arrival, if driver
was drunk
Vehicle
1 per vehicle
VIN number, weight class, body type of vehicle,
number of occupants, travel speed, initial contact
point, roll over, fire, fatalities, registration state,
license state of driver, type of license, driver height
and weight, previous convictions
Person
1 per person
injury level, age, sex, race, person type, injury
severity, seating position, restraint/helmet use or
misuse, airbag deployment, ejection and ejection path,
alcohol and drug tests, time of death, other related
factors
Data Source: Fatality Analysis Reporting System 2013

The FARS is produced through the National Highway Traffic Safety
Administration (NHTSA), and is a census compilation of fatal motor vehicle crashes
from all 50 states, the District of Columbia, and Puerto Rico since 1975. In order for
an incident to be reported as a FARS case, it must have occurred on a roadway that
is customarily open to the public, and must have resulted in at least one related
fatality within 30 days of the crash. Non-fatal crashes are not reported in the
database, nor are crashes that occur on private property or crashes where the
injured individual passes away more than 30 days after the collision. FARS data is
gathered by representatives in each state from police reports, death certificates and
coroner reports, vehicle registration and driver licensing files, hospital records, EMS
reports, vital statistics, and other state records; however no personal identifying
information is recorded to comply with the Privacy Act and allow all data files to be
made available to the public. The number of entries per state is dependent on the
aforementioned requirements to qualify as a fatal crash.
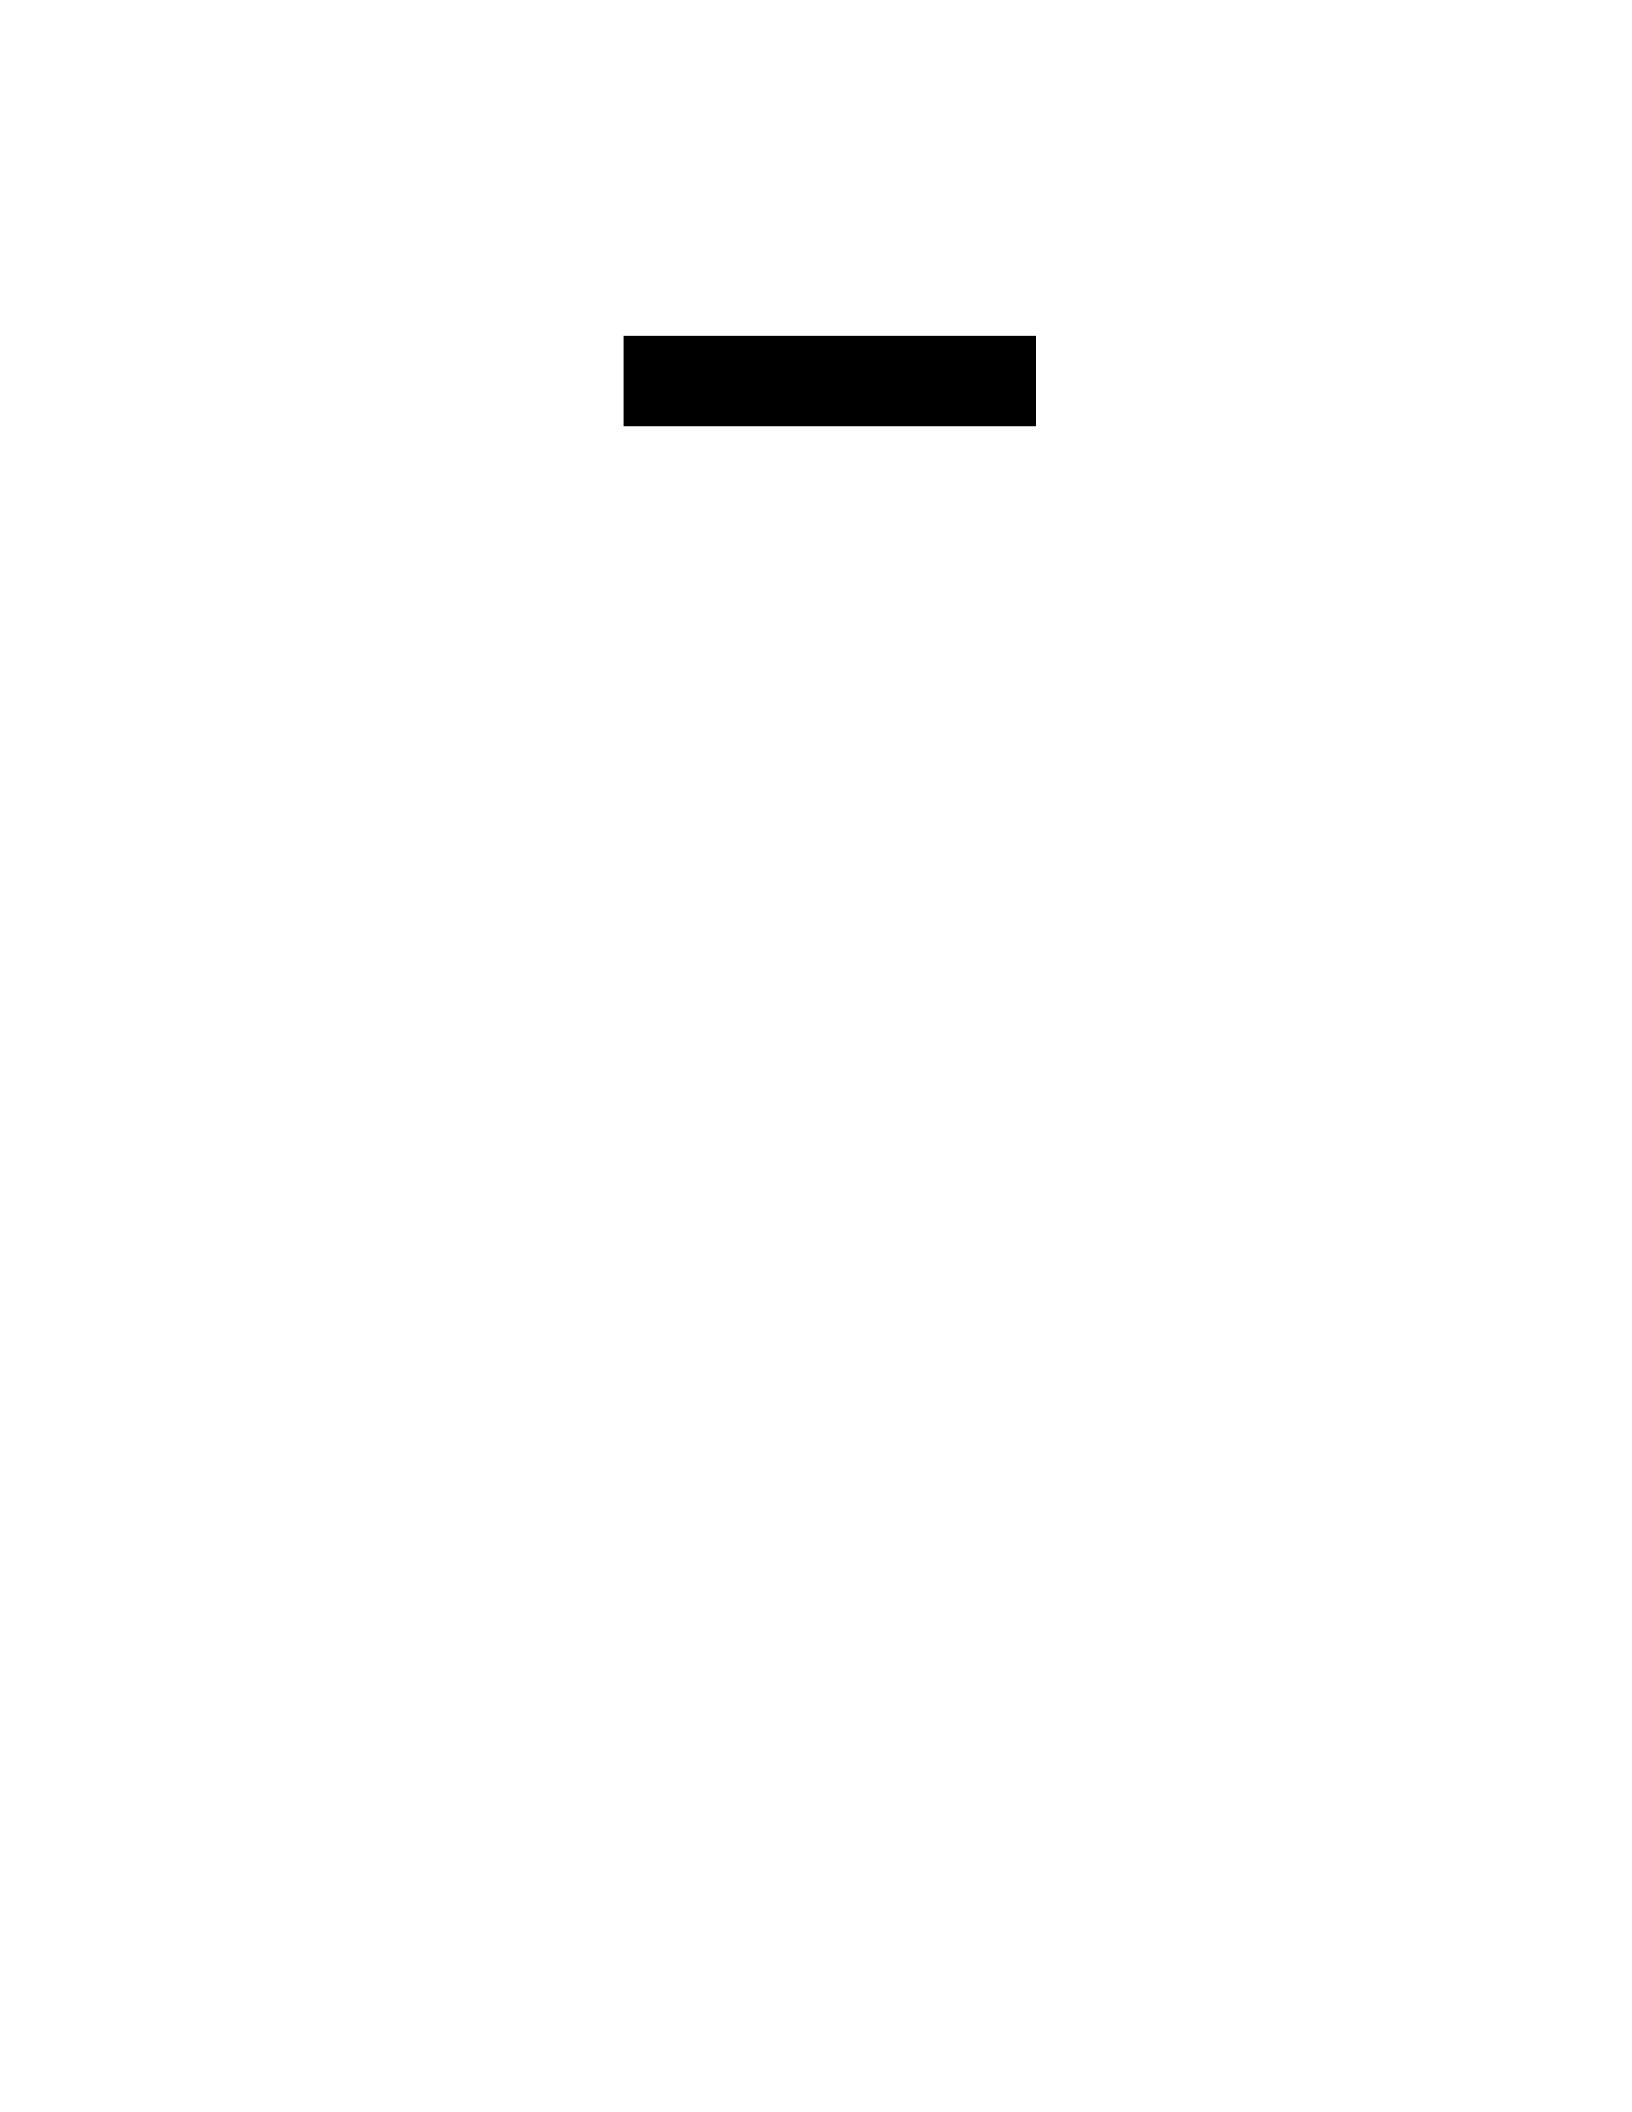
Fatality rates were calculated using the number of fatalities over a three year
period, to account for regression to mean in fatality levels, divided by the number
of vehicle miles of travel (VMT) for the same three years, obtained from the FHWA
Highway Statistics Series by state as shown in Equation 2.
Equation 2
The southeastern region calculations used the sum of the fatalities in the
eight southeastern states divided by the sum of the VMT for the corresponding
states, again using the three year totals to account for regression to mean
variations, as shown in Equation 3.
Equation 3
where i=1:8 is representative of each southeastern state.
In addition to fatalities, several other characteristics such as age and gender
of driver involved in fatal crash, lighting condition of fatal crash, and vehicle
occupancy of fatal crashes which are reported in the above mentioned files were
used to determine if correlations existed, and the levels of the correlations between
fatality rates by geography. This was done using a file that was created by
combining the same years, 2010 through 2012, that were used to calculate the
fatality rates for consistency. These files were then manipulated using Excel and
SPSS to find similarities, differences and correlations by state, national, and
southeastern regional levels.
3.1.2 Census Bureau Population Data
The U.S. Census Bureau conducts annual American Community Surveys
(ACS) data collection in all 50 states, the District of Columbia, and Puerto Rico. The
ACS uses a series of monthly samples to produce annual estimates at the state
level. The ACS is inclusive of not only the housing unit population but also, as of
2006, the group quarter population as well. In 2010, approximately 2.9 million
housing unit addresses were selected; in 2011 the sample size was increased to
3.54 million addresses per year. The sampling of the data is collected in two phases,
and the first phase consists of two stages. The first stage of the first phase consists

of dividing each county into five sub-frames, which are each a representative
sample of addresses in the county. The addresses are sorted and assigned to one of
the five sub-frames, to ensure that no household is sampled more than once in a
five-year period. The second stage of the first phase assigns the selected addresses
into a month within the year of the data collection. The sampling rate varies by the
size of the blocks in the sampling entity, with the blocks in the smallest sampling
entities at a rate of 15 percent, blocks in small sampling entities at a rate of
10percent and blocks in medium sampling entities at a rate of 7 percent. Blocks in
large sampling entities with predicted levels of completed interviews greater than
60 percent can have a sampling rate as small as 0.5 percent. The second phase of
sample selection gathers non-mailable (mail is directed to a post office box, or
address is incomplete) and non-responding addresses with computer assisted
telephone interviews and computer assisted personal interviews. In 2012, a total of
2.2 million of the estimated 132.5 million housing units completed the interview,
yielding a sample population of approximately 1.7 percent which covers about 93
percent of the population
(Census, 2014).
Once the sample is determined and the data is collected, “weights are used
to bring the characteristics of the sample more into agreement with those of the full
population by compensating for differences in sampling rates across areas”(Census,
2014). The ACS uses ratio estimation to make more precise estimations of
population by age, sex, race, etc. Adjustments are made to account for incomplete
interviews and vacant housing units. Multiyear estimation methodology involves

reweighing data over a three or five year period by pooling the data and using a
derivation of multiyear controls (Census, 2014).
The U.S. Census bureau was used for all population estimates and
calculations. This includes share of population calculations for specific age groups,
race, sex, and for weighing percentages of rates in the southeastern region. When
the population data was used from the U.S. Census Bureau a three-year estimate
from 2012 was used, to properly account for the corresponding data and fatality
rates which also used three years of data for all calculations.
3.1.3 Federal Highway Administration
The U.S. Department of Transportation has a department called the Federal
Highway Administration (FHWA) which publishes data and statistics at the national
and state level. One publication in particular which was used extensively for the
collection of data for analysis, is the annual Highway Statistics Series which
contains statistical information on bridges, highway infrastructure and travel,
travelers, vehicles, motor fuel, revenue and expenditures, conditions and safety,
and performance indicators (Highway Statistics Series, 2013). The majority of the
data reported in the Highway Statistics Series is submitted by individual states and
is analyzed for consistency against previous year’s data and against national data,
and is then prepared and processed through the Office of Highway Policy
Information within the FHWA.
The highway travel statistics reported in the Highway Statistics Series collects
annual average daily traffic (AADT) and centerline mileage in accordance with the
Highway Performance Monitoring System Field Manual (HPMS) (Highway Statistics

Series, 2013). In accordance with HPMS, AADT of all sections of interstate, National
Highway System and principal arterials are collected on a 100 percent basis;
however for minor arterials and collectors, sample AADT’s are collected and
expanded in accordance with HPMS. The per capita VMT in the
Highway Statistics Series is based on information from three sources, the
Nationwide Personal Transportation Survey, the Truck Inventory and Use Survey,
and the National Transportation Statistics report. Data from the Truck Weight Study
are collected in each state via weigh-in-motion systems.
In this thesis, the FHWA’s publications of the Highway Statistics Series were
used to calculate the total VMT by state, and were summed to calculate
southeastern region and national totals. The VMT data was subsequently used as a
denominator in the calculations of the fatality rates by state, southeastern region,
and at a national level (Highway Statistics Series, 2013).
3.2 Descriptive Data
Descriptive data collection was an imperative process in the analysis
performed to construct this thesis. The fatality rates that were calculated using the
above mentioned methodology were set as the dependent variable and the
descriptive characteristics that were collected and calculated were used as
independent variables to model the variation in fatality rates by geography. The
characteristics and the methodologies for each data source are below.

3.2.1 Federal Highway Administration
In addition to the VMT statistics used to calculate the dependent variable,
fatality rates, FHWA was also used to collect state level descriptive statistics such as
licensed drivers by age group, registered vehicles, and some ratios of these
statistics were calculated such as registered vehicles per licensed driver, which were
considered for use as descriptive independent variables in the fatality rate linear
regression model, presented later in this thesis, but were found to not be correlated
at an integrated level.
The licensed drivers’ statistics reported in the Highway Statistics Series
collects data from individual state departments of motor vehicles who issue drivers
licenses. There are some specifics about this data which should be noted. The ratio
of licensed drivers to total population should never be 1 due to the population who
choose not to become licensed or have mental or physical disabilities that limit their
ability to obtain a driver’s license. However the ratio may be higher than expected
due to some extenuating circumstances. There is a chance that some drivers may
be doubly counted if, for instance, they move from one state to another and get
licensed in their new state of residence; they will be double counted until their
original state license expires or until they relinquish that license. Other factors that
may not be represented in the statistics are drivers who drive without obtaining a
license, drivers who fraudulently obtain multiple licenses, and deceased individuals
whose licenses will usually be counted until expiration (Highway Statistics Series,
2013).
Vehicle registrations are another variable which are reported to the FHWA by
individual states, and states practices vary widely throughout the U.S. All states use

a vehicle registration renewal system which distributes the renewal workload
throughout all months of the year, with the exception of some vehicles in some
states which are renewed on a calendar year basis. For example, trucks in certain
weight classes may be registered by calendar year, while most personal vehicles are
generally registered annually in the birth month of the vehicle owner. To attempt
uniformity between states to the extent possible, information is reported as nearly
as possible on a calendar-year basis, with extra efforts put forth to exclude title
transfers and re-registrations which may occur in the pre-registration grace period.
It is possible that vehicles registered more than once in the same state, are
reported as multiple vehicles, although contrary to reporting protocol (Highway
Statistics Series, 2013).
3.2.2 Census Bureau Descriptive Demographic Data
In addition to the above mentioned population data collected from the
American Community Survey (ACS) through the U.S. Census Bureau, several other
descriptive characteristics statistics were also collected from the ACS (Census,
2014). Educational attainment, specifically the share of population over the age of
25 years who graduated from high school or obtained a high school equivalent
general education diploma, and the share of the same age group that obtained a
Bachelor’s degree or higher by state, southeastern region, and at the national level
were obtained. The split of sex of the population by geography was also explored as
a possible explanatory variable in the fatality rate variations. The share of elderly
population, those 65 years of age or older, was also determined by geography using
ACS data to try to distinguish which states had higher than national rates of aging

population. The share of residents born in their state of residency was gathered via
ACS data to give an idea of the share of population who were at least at one time
an unfamiliar driver on the roadway network, and also who might contribute to the
share of out of state visitors who would also be unfamiliar drivers on the roadway
network. Finally, the share of population below poverty level was explored as a
possible explanatory independent variable, given the poverty stricken population is
more likely to use vulnerable means of travel given the lower costs associated with
those means, such as walking or riding a bicycle.
Each of these above mentioned descriptive characteristics obtained using the
ACS data have allocation rates which are a measure of nonresponse. These
allocation rates vary by state and by variable, and range from about five percent to
about fifteen percent. The ACS methodology states that when the nonresponse rate
for a specific characteristic is high, bias can be introduced if the non-responses
differ substantially from given responses. Allocation rates are calculated by dividing
the number of nonresponses allocated for a specific characteristic in a specific state
divided by the total number of responses for that characteristic in that state times
one hundred to give a share, as shown in Equation 4.
Equation 4
3.2.3 Fair Isaac Company (FICO)
While the literature review from a previous section in this thesis states that
insurance companies use only certain characteristics of an individual’s credit score
to determine their credit based insurance score, the concept behind the correlation
of a credit score and likelihood to behave in a risky manner in other aspects in life
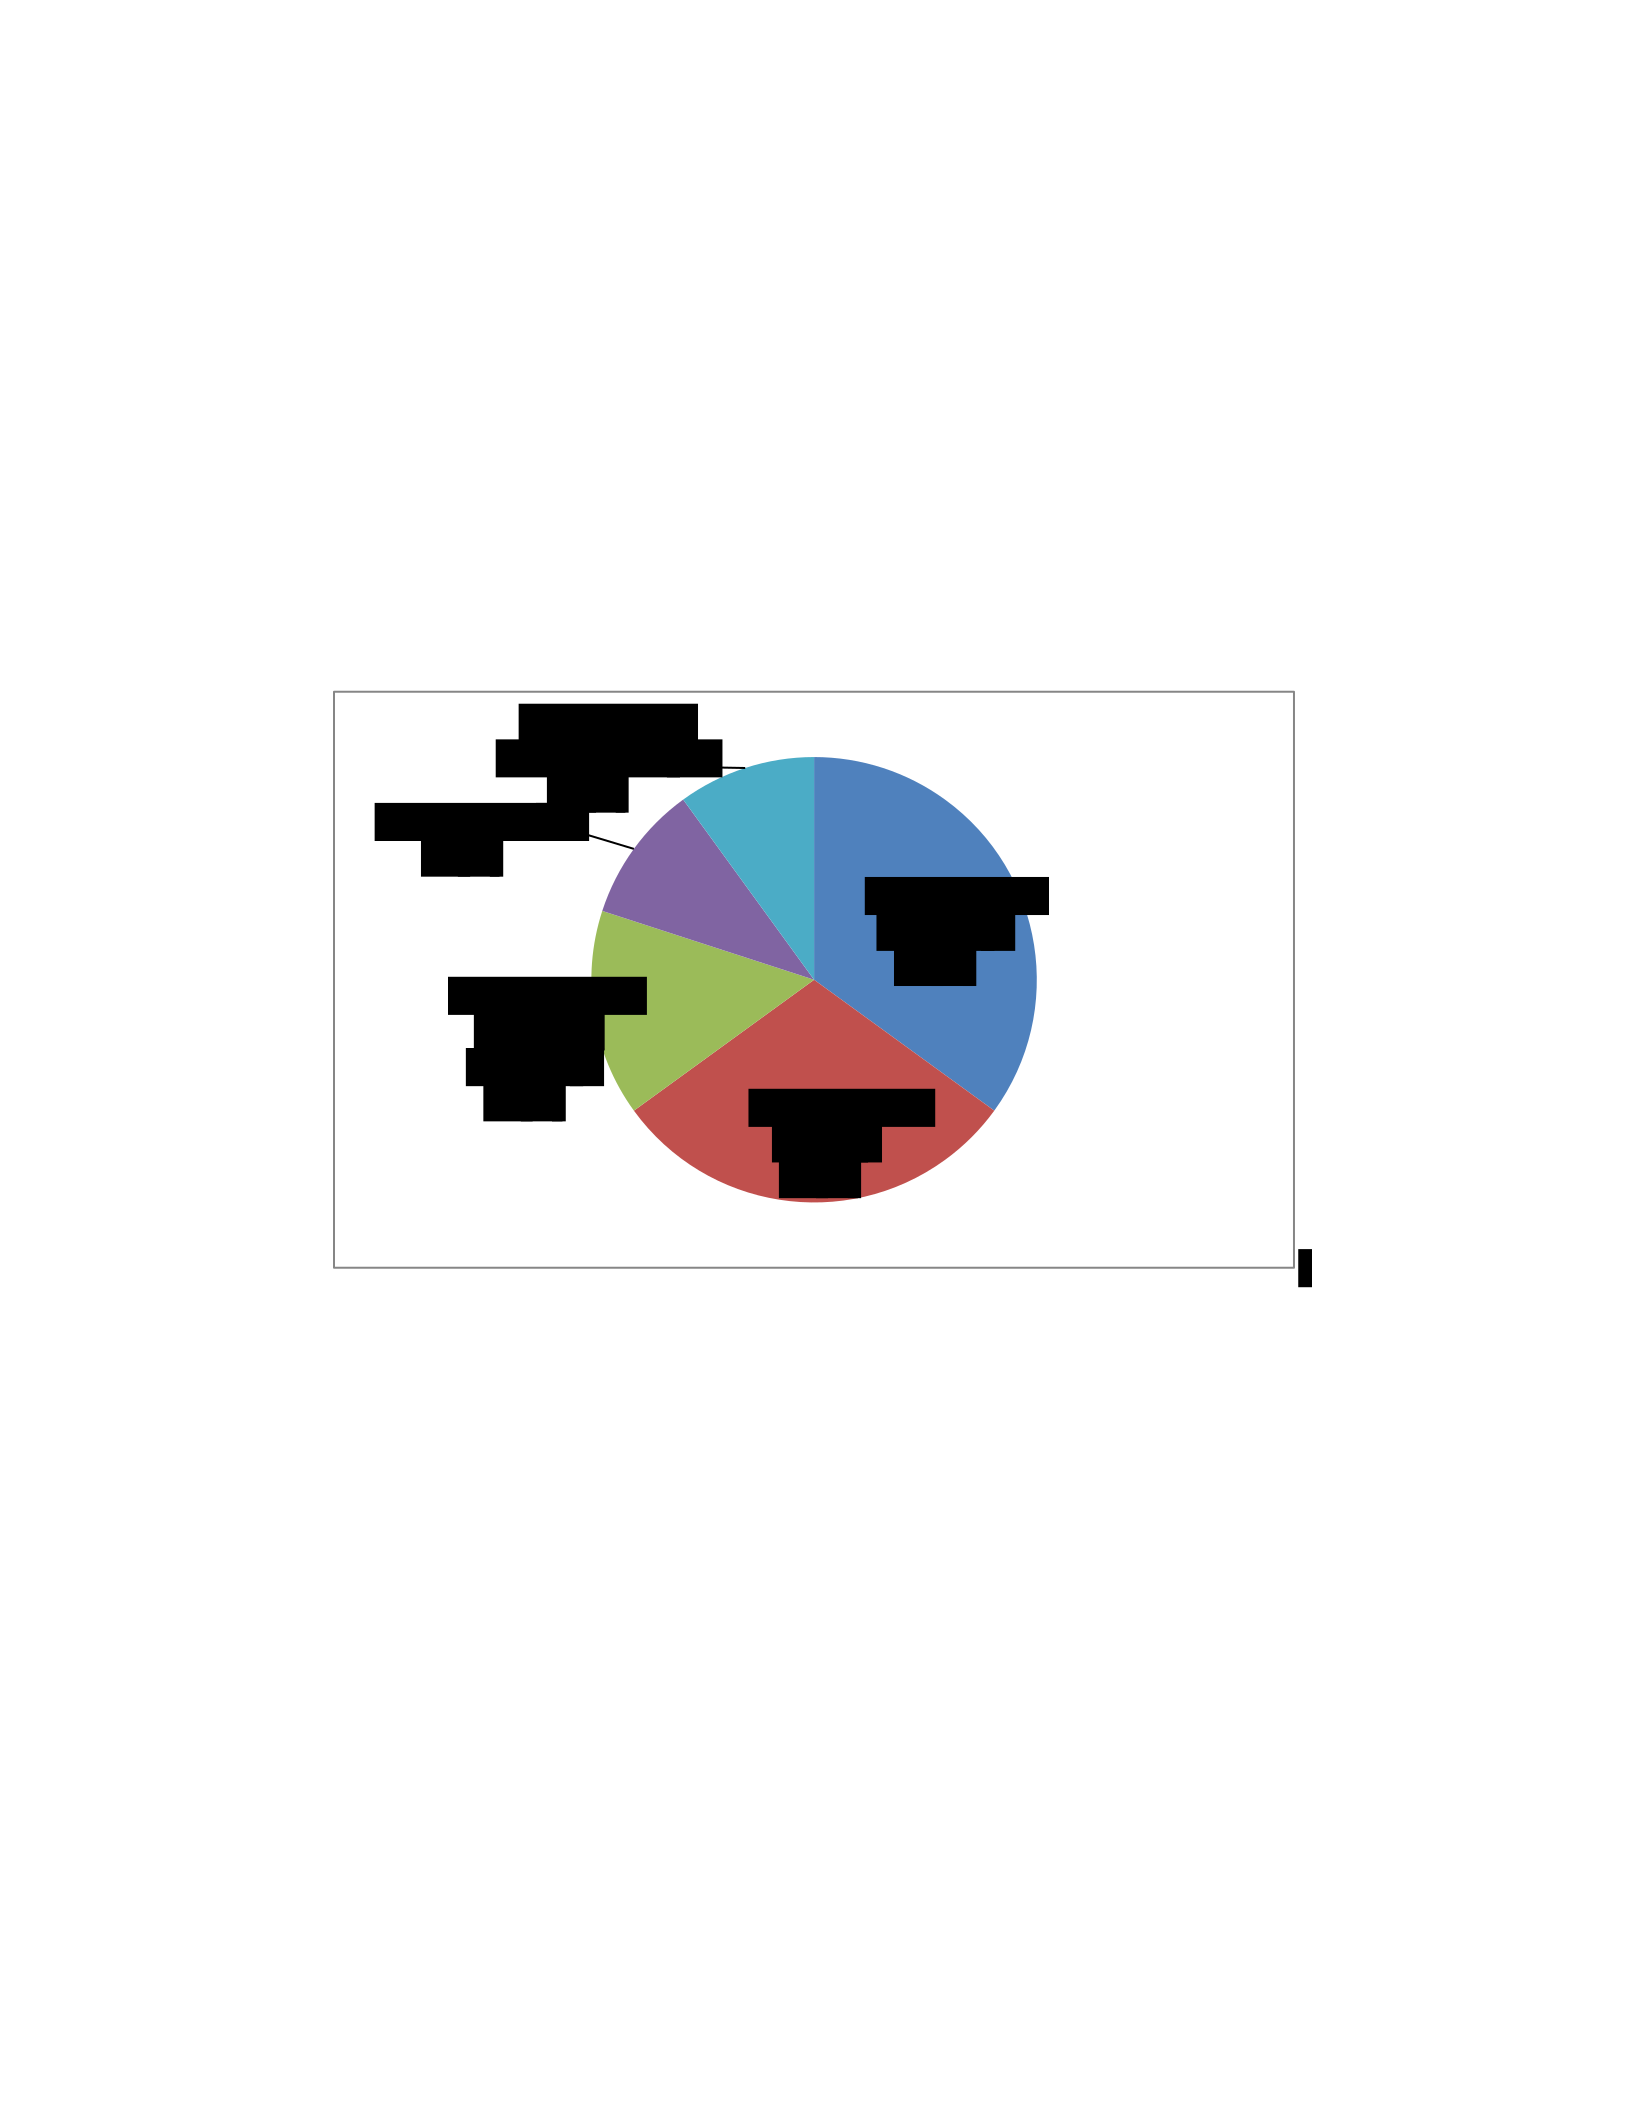
should be cohesive using a general credit score as well. The FICO credit score is
comprised of varying importance of five factors; payment history (35%), amounts
owed (30%), length of credit history (15%), new credit (10%) and types of credit
used (10%) as shown in Figure 5 (MyFICO, 2015). The Equal Credit Opportunity Act
(ECOA) was enacted in 1974 and makes it unlawful for a creditor to use race, color,
religion, origin, sex, or marital status or age as a basis to determine an individual’s
credit score.
Figure 5 Credit Score Factors. Data Source: MyFICO.com
The credit trends, average credit score by state, were collected through
Credit Karma, which is an internet source that provides credit scores to their
members, in addition to providing the average credit score trends by state, age and
domain. This is done by taking their members and performing crosstab analyses
with credit scores and the perspective characteristics. The result yields that the
state with the lowest average credit score is Mississippi with a score of 612, and the
state with the highest average credit score is Hawaii with a score of 659 (Credit
Payment
History
35
%
Amounts
Owed
30
%
Length of
Credit
History
15
%
New Credit
10
%
Types of
Credit Used
10
%

Karma, 2013).
3.2.4 Federal Department of Health and Human Services The
Federal Department of Health and Human Services has a department called the
Substance Abuse and Mental Health Services Administration (SAMHSA) which
conducts an annual National Survey on Drug Use and Health (NSDUH) to
population age 12 years and older. The NSDUH generates estimates on a national
state and sub-state level to describe patterns of prevalence of alcohol, drug and
tobacco use and mental health disorders in the U.S. The 2012 survey data used
in the analysis of this thesis was a compilation of data collected from 136,147
respondents in all 50 states and the District of Columbia, with an overall response
rates ranging from 45.8 percent to 75.2 percent with a median response rate of
61.5 percent (SAMHSA, 2013).
The survey state small area estimation obtained using the survey-weighted
hierarchical Bayes estimation methodology models aggregate data at the state and
national level. The Bayesian confidence interval for the NSDUH is a 95 percent
confidence interval, which is asymmetric meaning that the size difference between
the lower limit and the estimate is not equal to the size difference between the
upper limit and the estimate. The asymmetry is appropriate when dealing with
small percentages, such as those in the NSDUH, and help to adjust for
overestimating or underestimating the actual precision levels of the data. It should
also be noted that if two states have overlapping confidence intervals that does not
indicate equivalency of the state estimates. It is also noteworthy that correlated
substance use cannot be properly extracted at a small area level, but can be done

at a national level. For example, subtracting cigarette use from tobacco use at a
state level could give negative results, which would be misleading and should be
avoided, however making that same substitution at the national level is valid and
would indicate proper non-cigarette tobacco use (SAMHSA, 2013). For this
thesis, the NSDUH was used to collect and compare state and national data by age
group for marijuana use in the past year, illicit drug, alcohol, binge alcohol,
tobacco product, and cigarette use in the past month, in addition to serious mental
illness, any mental illness, thought of suicide, and depressive episodes in the past
year. All of the shares were tabulated and the correlations to fatality rates by state
were determined.
3.2.5 Center for Disease Control and Prevention (CDC)
The CDC is also under the umbrella of the Federal Department of Health and
Human Services. The CDC produces a uniform questionnaire called the Behavioral
Risk Factor Surveillance System (BRFSS) which was first conducted in the early
1980’s, and became a nationwide surveillance system in 1993. The BRFSS
conducted more than 500,000 interviews nationally in 2011, making it the largest
phone survey in the world. The data used in this thesis was from data collected in
2011 and 2012, which used more a sophisticated methodology than the previous
years. The new methodology uses iterative proportional fitting, with weights applied
through several strata including age, gender, race/ethnicity, educational attainment,
marital status, property ownership, and telephone ownership (CDC,

2013). In addition, cellular telephone interview standards have been accepted as of
2011; and due to the multiple methodology changes which occurred in 2011, any
pre-2011 data should not be directly compared to 2011 and subsequent data.
“Response rates for BRFSS are calculated using standards set by the
American Association of Public Opinion Research Response Rate Formula #4.
The response rate is the number of respondents who completed the survey
as a proportion of all eligible and likely-eligible persons. The mean survey
response rate for all states, territories and Washington, DC, in 2013 was 46.4
and ranged from 29.0 to 60.3. Response rates for states included in this
analysis had a median of 9.1% and ranged from 4.9% to 21.2%. For detailed
information see the BRFSS Summary Data Quality Report (CDC, 2013).”
The response rate Formula 4 defined in the American Association of Public
Opinion Research includes partial interviews as respondents and also allocates cases
where the eligibility is unknown. The formula used the summation of complete and
partial interviews as the numerator, divided by a denominator which is the
summation of complete and partial interviews plus the summation of the refused
non-contact, and other interviews plus the estimated proportion of cases of
unknown eligibility that are eligible multiplied by the sum of unknown if household
is occupied and unknown other interviews as shown in Equation 5 (AAPOR, 2011).
Equation 5
where RR = response rate
I = complete interview
P = partial interview

R = refusal and break-off
NC = non-contact
O = other
UH = unknown if household is occupied
UO = unknown other.
From this survey, the data collected for comparison to fatality rates by
geography included Alcohol use in the past 30 days, body mass index (BMI),
specifically BMI classifications such as underweight, normal weight, overweight, and
obese, and self-described overall general health classification, specifically
selfdescribed excellent and poor health conditions.
3.3 Methodology of Data Analysis
To initially determine the likelihood of correlation between the different
risktaking and other socio-demographic and socio-economic characteristics and
fatality rates by geography, a very broad based collection of data from multiple
sources occurred over approximately a nine month time period. The data was
collected from all of the above mentioned sources. In addition, some additional
sources were initially explored but not included in this thesis because they were
found to have insignificant correlations early in the data collection stages. For the
exploratory data collection the first correlations were calculated using Pearson
Correlation
Coefficients comparing the array of data of average fatality rates by state over the
three year period to each of the above mentioned independent variables, and if the
correlation coefficient was of a magnitude smaller than 0.30, positive or negative, it
was disregarded and considered to be of little significance to the research. Following

the collection of data, and the calculations of correlation coefficients, several
characteristics were obtained and used to complete bivariate correlation analyses
and a regression model was eventually formed to estimate the fatality rates by
specific correlated characteristics. The intention is to understand the strength of the
relationship between the respective variables and fatality rates.
3.3.1 Bivariate Pearson Correlation Analyses
Correlation coefficients are indicators of how closely plotted data fits a
straight line. The closer the correlation coefficient is to a magnitude of one, the
better the fit of the data to a straight line. Whether the correlation coefficient is
positive or negative indicates the sign of correlation. For instance, if a correlation
coefficient is calculated to be -0.9 there is a strong negative correlation between
the variables indicating as one variable increases, the opposite variable decreases
proportionately. On the other hand, if the correlation coefficient is calculated to be
0.9, then the relationship between the two variables is indicated to be a strong
positive correlation, meaning as one characteristic increases, the other
characteristic also increases proportionately. Using a 95 percent two-tailed
confidence interval a correlation coefficient is said to be of moderate statistical
significance if the magnitude of the Pearson Correlation Coefficient is larger than
0.3, positive or negative (Explorable.com). Alternatively, any Pearson Correlation
Coefficient that is less than 0.3 in magnitude is statistically insignificant at the 95
percent confidence interval. The confidence interval indicates the probability of an
estimate being representative of the individual sample 95 percent of the time. The
Pearson Correlation Coefficient is calculated as shown in Equation 6.

Equation 6
where r = Pearson Correlation Coefficient
X = fatality rate
Y = each independent variable individually
= the average fatality rate
= the average of each independent variable.
A Bivariate Pearson Correlation analysis was calculated in SPSS with each of
the above mentioned characteristics entered by state. This correlation analysis was
used to determine the characteristics which had significant correlations not only to
the fatality rates by state, but also between each characteristic. For instance, it is
known from the literature review previously performed that education levels and
poverty levels are greatly negatively correlated, with higher education levels
indicating a much lower probability of living in poverty. Given the strength of the
correlation between the two characteristics, only one should be used in the linear
regression model to estimate fatality rates by risk-taking characteristics, with the
choice of which variable to use depending on the interactions with other variables
used in the model. This type of comprehensive analysis was performed throughout
all previously listed characteristics to determine which characteristics best estimates
fatality rates by geography at a state level.
It is noteworthy that the correlation between two variables does not indicate
causation. For example, while credit score is correlated with the safety of an
automobile, the crash is not caused because an individual has a poor credit score.
Thus correlation and causation have two different meanings and should not be used
interchangeably. On the other hand, this does not mean that fatality rates cannot

be affected by the implementation of specific goals to improve specific
characteristics. For instance, risk-taking behavior reduces with an increase in
education levels, therefore it is arguable that if more of the population becomes
more educated and is counseled on the consequences of risk-taking behavior, the
risk-taking behavior may decrease, thus decreasing the probability of a fatal crash
occurring. More reasoning behind this will be presented in the data analysis and
conclusion portions of this thesis.
3.3.2 Regression Model
A linear regression model is used to describe the relationship between a
dependent variable and one or more independent variables. Linear regression
models use the same concept introduced in algebra as an equation of a line, as
shown in Equation 7. Linear regression was used with the assumption that all
variables were linearly correlated with the fatality rates at a state level. Nonlinear
correlations were initially calculated but resulted in extremely similar correlation
coefficients there for a linear regression was used.
Equation 7
where Y = the dependent variable, in this case fatality rate
a = a constant each = independent variable each =
coefficient for independent variable .
The regression models calculated for this thesis were estimated using a 95
percent confidence interval to determine statistical significance. The Pearson

Correlation Coefficients mentioned in the previous section 3.3.1, were used to
determine which variables should be considered for input into the linear regression
model. Once the original regression model was estimated the magnitude of the t
statistic score was compared to a critical t statistic score of 1.28 which is associated
with a one-tailed confidence interval of 90 percent. This 90 percent confidence
interval indicates that the probability of each parameter in the regression model is
statistically significant 90 percent of the time. The coefficient of each of the
variables in the linear regression model represents the change in fatality rates per
each increment in the given variable, given all else remains constant.
When using a linear regression model to describe a dependent variable, a
null hypothesis is inherently being tested. The null hypothesis is a statement that all
else remaining the same, that specific independent variable does not influence the
value of the dependent variable. If the magnitude of the t statistic score is greater
than or equal to the critical t statistic score associated with the given confidence
interval, then the null hypothesis can be rejected. A null hypothesis is never
accepted, but rather can fail to be rejected. If there is a failure to reject the null
hypothesis at a given confidence interval, that variable is inherently insignificant in
influencing the dependent variable. The specific calculated linear regression model
used to estimate the fatality rates by geography will be given in the following
chapter.

CHAPTER 4:
DATA ANALYSIS
The variables that were collected and analyzed were mentioned in the
previous chapter on data collection and methodology. This chapter will focus on the
specific data analyses that were performed, and the significance or insignificance
that each variable was found to have. It is important to note that while some
variables have significant Pearson Correlation Coefficients in the initial stages of
comparison, when all significant variables were considered for the regression model,
many were found to be statistically insignificant at an overall level. Therefore, while
twenty-five characteristics were calculated and compared to fatality rates, only six
variables were used to construct the linear regression model, three of which can be
considered to be classified as risk-taking behaviors, and three which are descriptive
or demographic characteristics not necessarily associated with risk-taking
behaviors. These non-risk-taking behaviors were still important to include in the
regression model to include as many variables as possible, which increases the
accuracy of the estimate model and reduces unobserved component captured in the
error term.

4.1 Fatality Variation across Geography
Although the NHTSA reports fatality rates, not only per VMT, but also per
population, they do not report fatality rates for the southeastern region specifically.
The rates are also yearly rates, and for the purposes of accounting for the
regression to mean, the fatality rates for three years were calculated. A simple
average of fatality rates would not be precisely representative of the three year
average fatality rate, thus the number of fatalities was recorded from the NHTSA
FARS files, and the VMT was recorded from the FHWA Highway Statistics Series for
each state over each year of analysis from 2010 to 2012. For the calculation of the
southeastern region fatality rate the sums of fatalities over three years in each of
the eight southeastern states were summed. The same procedure was done to the
VMT rates for each of the eight states, and the summation of the fatalities was
divided by the summation of the VMTs. The eight states in the southeastern region
include Alabama, Florida, Georgia, Kentucky, Mississippi, North Carolina, South
Carolina, and Tennessee. These averaged fatality rates were used as the dependent
variable in all analyses regarding this thesis. The fatality rates by state, national
average and southeastern region calculated from the FARS database are all listed in
Table 7. It should be noted that every state in the southeastern region of the U.S.
has a higher fatality rate than the national average fatality rate, and southeastern
states represent three of the top six states in the highest fatality rates. These are
unfortunate statistics, and leave a massive amount of room for improvement on the
safety of the roadway network in the southeastern U.S.
Table 7 Fatality Rates by State
State
Fatality
Rate
State
Fatality
Rate
State
Fatality
Rate
District of Columbia
0.62
Oregon
0.98
Texas
1.34
Massachusetts
0.65
Indiana
0.99
Arizona
1.34
Minnesota
0.69
Wisconsin
1.00
Kansas
1.35
Washington
0.79
Nebraska
1.01
Alabama
1.35
New Jersey
0.80
Maine
1.07
New Mexico
1.39
Rhode Island
0.82
Nevada
1.08
Tennessee
1.40
Connecticut
0.83
Total U.S.
1.11
South Dakota
1.42
New Hampshire
0.84
Georgia
1.12
Oklahoma
1.45
California
0.87
Hawaii
1.13
Wyoming
1.48
Maryland
0.88
Delaware
1.16
Louisiana
1.53
Illinois
0.89
Idaho
1.17
North Dakota
1.54
Utah
0.90
Missouri
1.17
Kentucky
1.55
New York
0.91
Iowa
1.18
Mississippi
1.58
Virginia
0.93
North Carolina
1.23
Arkansas
1.67
Vermont
0.94
Florida
1.26
South Carolina
1.70
Ohio
0.96
SE region
1.31
West Virginia
1.73
Michigan
0.97
Pennsylvania
1.31
Montana
1.74
Colorado
0.98
Alaska
1.32
Note: Yellow indicates the states in the southeastern region, orange indicates the
southeastern average, and green indicates the national average.
Data sources: Fatality Analysis Reporting System, 2010-2012 for data on fatalities;
FHWA’s annual Highway Statistics for VMT.
4.2 Risk-Taking Variations across Geography
Unfortunately for the southeastern region of the U.S. fatality rates are not
the only characteristics that are chart toppers. The following three risk-taking
characteristics are all characteristics which every state in the southeastern region
ranks worse than the national average, and each of the characteristics are
presented in their respective tables in ascending order; therefore for a characteristic

such as credit score, each of the southeastern states have values lower than the
national average, whereas for poor overall health, each of the southeastern states
have shares higher than the national average. The states in the southeastern U.S.
also have some of the worst credit scores in the nation, taking all three top spots
for lowest credit scores in the nation starting from the lowest, Mississippi with an
average FICO credit score of 612, South Carolina is next to lowest with an average
score of 621, and Alabama comes in third with an average of 623. In addition, all
eight southeastern states rank within the lowest nineteen states for credit scores,
the highest of which is Florida at 637, which is still below the national average of
640, as shown in Table 8. This is an indication that each of the southeastern states
has average FICO credit scores below the national average credit score (FICO,
2013).
Another factor where the southeastern states rank worse than the nation is
overall poor health as indicated by the BRFSS. All eight states in the southeastern
region have higher rates of poor health than the national average of 4.4 percent as
shown in Table 9. The southeastern average share of adult population with poor
health is 6.1 percent. Bachelor’s degree or higher educational attainment is yet
another characteristic where every state in the southeastern region ranks worse
than the national average share. For the adult population 25 years of age or older,
the national share of population that has obtained at least a Bachelor’s degree is
28.8 percent. For that same age group in the southeastern states, the average
share is 25.5 percent, and the state with the highest share in the southeastern
region is Georgia, with 28.0 percent of the population with a Bachelor’s degree or
higher as shown in Table 10.
Table 8 Credit Scores by State
State
Credit
Score
State
Credit
Score
State
Credit
Score
Mississippi
612
Michigan
636
South Dakota
646
South Carolina
621
Florida
637
Vermont
646
Alabama
623
Nevada
637
Oregon
647
Arkansas
624
Maryland
638
Rhode Island
647
Louisiana
624
Idaho
639
District of Columbia
648
Kentucky
627
Wisconsin
639
North Dakota
648
Texas
627
Wyoming
639
Alaska
650
West Virginia
628
Total U.S.
640
New Hampshire
650
Oklahoma
629
Arizona
640
California
651
Tennessee
629
Illinois
640
Connecticut
651
Georgia
630
Kansas
640
Washington
651
SE region
630
Pennsylvania
640
New Jersey
653
Indiana
631
Iowa
641
New York
654
Missouri
632
Virginia
643
Minnesota
655
New Mexico
632
Montana
645
Maine
658
North Carolina
632
Utah
645
Massachusetts
658
Ohio
634
Colorado
646
Hawaii
659
Delaware
635
Nebraska
646
Note: Yellow indicates the states in the southeastern region, orange indicates the
southeastern average, and green indicates the national average. Data Source:
CreditKarma.com, 2012
Table 9 Overall Poor Health by State
State
Poor
Health
State
Poor
Health
State
Poor
Health
Minnesota
2.9
New Jersey
4.0
Texas
5.0
District of Columbia
3.0
North Dakota
4.0
Oregon
5.2
South Dakota
3.0
Virginia
4.0
Florida
5.3
Colorado
3.1
Wisconsin
4.1
Missouri
5.4
Utah
3.1
Washington
4.2
New Mexico
5.4
Connecticut
3.2
Wyoming
4.2
North Carolina
5.4
Maryland
3.2
Ohio
4.3
Indiana
5.5
Hawaii
3.3
Arizona
4.4
South Carolina
5.9
Idaho
3.4
Delaware
4.4
SE region
6.1
Iowa
3.4
Nevada
4.4
Oklahoma
6.3
Massachusetts
3.4
Total U.S.
4.4
Louisiana
6.5
Table 9 Continued
New Hampshire
3.4
Alaska
4.5
Alabama
7.3
Vermont
3.4
California
4.6
Kentucky
8.0
Nebraska
3.5
Georgia
4.6
Arkansas
8.2
Kansas
3.8
Montana
4.7
Mississippi
8.3
Rhode Island
3.8
Pennsylvania
4.7
Tennessee
8.5
Illinois
4.0
Michigan
4.8
West Virginia
8.8
Maine
4.0
New York
4.8
Note: Yellow indicates the states in the southeastern region, orange indicates the
southeastern average, and green indicates the national average.
Data Source: BRFSS, 2011-2012
Table 10 Bachelor’s Degree or Higher by State
State
Higher
Degree
State
Higher
Degree
State
Higher
Degree
West Virginia
18.3
Missouri
26.2
Kansas
30.3
Arkansas
20.1
South Dakota
26.2
Utah
30.3
Mississippi
20.1
Florida
26.4
California
30.7
Kentucky
21.5
Texas
26.7
Rhode Island
31.3
Louisiana
21.8
Wisconsin
26.8
Illinois
31.4
Nevada
22.4
Arizona
26.9
Washington
31.9
Alabama
22.6
North Dakota
27.2
Minnesota
32.6
Indiana
23.2
North Carolina
27.3
New York
33.2
Oklahoma
23.5
Alaska
27.5
New Hampshire
33.7
Tennessee
23.8
Pennsylvania
27.5
Vermont
34.8
Wyoming
24.7
Maine
27.9
Virginia
35.2
Idaho
25.1
Georgia
28.0
New Jersey
35.8
South Carolina
25.1
Nebraska
28.5
Connecticut
36.5
Ohio
25.2
Montana
28.7
Maryland
36.8
SE region
25.5
Total U.S.
28.8
Colorado
37.0
Iowa
25.7
Delaware
28.9
Massachusetts
39.4
New Mexico
25.8
Oregon
29.7
District of Columbia
52.4
Michigan
25.9
Hawaii
30.1
Note: Yellow indicates the states in the southeastern region, orange indicates the
southeastern average, and green indicates the national average.
Data Source: U.S. Census Bureau, 2010-2012
When it comes to the number of states in the southeast that have a larger
share of adult smokers than the national average, the region is not quite as bad as
the fatality rate rankings and the credit score rankings. However, only one
southeastern state, Florida (16.8 percent), has a smaller share of adult smokers
than the national average (18.2 percent). In the southeastern states the average
share of adult population that smokes is 20.0 percent as shown in Table 11 (BRFSS,
2012). Trends of alcohol use in the past 30 days are a bit more promising. The
average share of the adult population in the southeastern states that reported
drinking alcohol in the past month was 46.6 percent, which is lower than the
national average of 54.5 percent. As a matter of fact, only one southeastern state,
Florida (54.7 percent), had a higher share of alcohol drinkers than the national
average as shown in Table 12 (BRFSS, 2012).
Table 11 Adult Tobacco Users by State
State
Tobacco
Users
State
Tobacco
Users
State
Tobacco
Users
Utah
10.3
Illinois
18.0
Wyoming
20.6
California
12.5
Minnesota
18.0
Pennsylvania
21.0
Hawaii
13.3
Total U.S.
18.2
North Dakota
21.2
Connecticut
15.5
Nebraska
18.5
Michigan
21.4
New Jersey
15.7
Wisconsin
18.7
Alabama
21.5
Texas
15.9
District of Columbia
18.8
Indiana
21.9
Washington
16.1
Georgia
18.8
South Carolina
22.0
New Hampshire
16.2
Montana
19.0
Missouri
22.1
Arizona
16.3
Virginia
19.0
Alaska
22.6
Maryland
16.4
New Mexico
19.1
Ohio
23.4
Massachusetts
16.6
Nevada
19.4
Louisiana
23.5
New York
16.6
Iowa
19.5
Oklahoma
23.7
Vermont
16.6
Delaware
19.6
Tennessee
24.3
Florida
16.8
South Dakota
19.6
Mississippi
24.8
Idaho
17.2
Kansas
20.0
Arkansas
25.9
Oregon
17.3
Maine
20.2
Kentucky
26.5
Rhode Island
17.4
SE region
20.2
West Virginia
27.3
Colorado
17.7
North Carolina
20.3
Note: Yellow indicates the states in the southeastern region, orange indicates the
southeastern average, and green indicates the national average.
Data Source: BRFSS, 2012
Table 12 Adult Alcohol Drinkers by State
State
Alcohol
Users
State
Alcohol
Users
State
Alcohol
Users
Utah
30.7
Idaho
49.6
Nebraska
57.5
West Virginia
34.0
Arizona
51.5
South Dakota
57.8
Tennessee
37.5
Kansas
51.5
Maine
58.6
Kentucky
38.2
Virginia
52.0
New Jersey
58.6
Mississippi
38.4
Wyoming
53.0
Washington
58.7
Arkansas
39.8
Ohio
53.3
Montana
58.8
Alabama
40.3
Nevada
54.1
North Dakota
61.0
Oklahoma
42.0
Pennsylvania
54.4
Oregon
61.0
North Carolina
44.3
Maryland
54.5
Colorado
61.9
SE region
46.6
Total U.S.
54.5
Connecticut
62.6
Georgia
47.1
Florida
54.7
Rhode Island
62.6
New Mexico
48.3
Alaska
55.4
Vermont
62.9
Indiana
48.5
New York
55.4
Massachusetts
63.6
Missouri
48.5
California
55.5
Minnesota
63.6
South Carolina
48.5
Michigan
56.6
New Hampshire
63.7
Louisiana
49.0
Delaware
57.1
District of Columbia
64.3
Hawaii
49.3
Illinois
57.2
Wisconsin
64.6
Texas
49.3
Iowa
57.2
Note: Yellow indicates the states in the southeastern region, orange indicates the
southeastern average, and green indicates the national average. Data Source:
BRFSS, 2012
Serious mental illness is another characteristic that was explored as being
associated with increased risk-taking behaviors, thus possibly associated with traffic
fatality rates. For adults 26 years of age and older, the average share of the
population that had a serious mental illness was higher in the southeastern region
than the national average share, however three of the southeastern states had
lower shares of mental illness in that age group, Alabama, Florida, and Georgia, as
shown in Table 13.
Table 13 Adults (26+) with Serious Mental Illness by State
State
Mental
Illness
State
Mental
Illness
State
Mental
Illness
Maryland
3.16
Delaware
4.10
Montana
4.58
New Jersey
3.16
Total U.S.
4.14
Ohio
4.62
Illinois
3.24
Minnesota
4.16
Missouri
4.66
Connecticut
3.28
Texas
4.16
Tennessee
4.66
Hawaii
3.32
Wisconsin
4.16
Idaho
4.69
South Dakota
3.51
Nebraska
4.18
Oregon
4.81
New York
3.71
Wyoming
4.19
North Carolina
4.84
Alabama
3.79
Massachusetts
4.21
Mississippi
4.86
New Hampshire
3.79
Arizona
4.26
Washington
4.90
Colorado
3.83
Alaska
4.27
Maine
4.96
California
3.87
New Mexico
4.30
Rhode Island
4.99
Virginia
3.90
SE region
4.32
Kentucky
5.03
District of Columbia
3.95
Louisiana
4.33
Oklahoma
5.14
Florida
3.98
Iowa
4.37
West Virginia
5.27
Pennsylvania
4.01
Kansas
4.40
Utah
5.36
Georgia
4.02
South Carolina
4.41
Vermont
5.36
Nevada
4.05
Indiana
4.44
Arkansas
5.41
North Dakota
4.05
Michigan
4.58
Note: Yellow indicates the states in the southeastern region, orange indicates the
southeastern average, and green indicates the national average. Data Source:
NSDUH, 2012
4.3 Correlations with Fatality Rates
Pearson Correlation Coefficients were calculated for each explored
characteristic by state to get an idea of how much the characteristic related not
only to fatality rates, but also to other characteristics. This is an important step in
the analysis because a regression model should not include two highly correlated
variables as independent variables. Including two highly correlated variables in a
regression model will skew the results of the model and make the output of the
model less reliable. While all correlations that were above 0.3 are considered
statistically significant at a 95 percent confidence interval, not all statistically
significant characteristics remained significant when multiple characteristics were
entered into the regression model. Therefore, some of the variables that are shown
below to have individual statistical significance to the fatality rates by state are not
included in the final regression model used to estimate the fatality rates. All

correlations between fatality rates and characteristics are presented in Table A1
located in the appendix.
4.3.1 Credit Score
The average credit score for each state and the nation as a whole was
collected and the weighted average for the southeastern region was calculated
using a population based weighted average over the eight southeastern states
(CreditKarma, 2015). The Pearson Correlation Coefficient was calculated between
the average credit scores and the average fatality rates. As noted previously, the
closer the magnitude of the coefficient is to one, the stronger the correlation
between the two arrays of values. The Pearson Correlation Coefficient between
credit scores and fatality rates was calculated to be -0.643 which is statistically
significant at the 95 percent confidence interval. This is indicative of a strong
negative correlation. This means that with 95 percent confidence, average credit
scores are related to fatality rates at the state level. Credit score is one
characteristic that may help to explain the increased levels of fatality rates in the
southeastern region when compared to the rest of the U.S. because the credit
scores are significantly lower in the southeastern states also.
4.3.2 Smoking
The average share of the adult population that has used any tobacco product
in the past thirty days (of the survey) was calculated using the BRFSS data and the
NSDUH data, although the results were nearly identical between the two data

sources, the BRFSS data was used because the methodology of the survey
contained a larger sample size. The Pearson Correlation Coefficient was calculated
comparing tobacco use among adults to fatality rates by state, and was found to be
0.641, indicating that there is a moderate statistically significant correlation at a 95
percent confidence interval. This correlation can be interpreted as meaning states
with a higher share of adult smoking population also have higher fatality rates. This
is a correlation and not causation, meaning that while smoking does not cause
motor vehicle crashes, smoking is considered a risk-taking behavior. As
hypothesized, as the share of the adult population that uses tobacco increases, the
share of adults who are likely to behave in a risky manner also increases, thus the
number of fatal crashes increases.
4.3.3 Alcohol Consumption
The average share of the adult population that has consumed an alcoholic
beverage in the past month was calculated using the BRFSS data collected over a
two year period. This is self-reported alcohol use, so the share may be under
representative of the actual share of the adult population that has had a drink,
because some individuals that are classified as adults but are not of legal drinking
age may be less apt to tell the truth in a voluntary survey. In addition, several
counties in the southeastern region of the nation are dry counties which prohibit the
sale, distribution, and consumption of alcohol, which may also lead to inaccuracies
when referring to self-reporting in a survey. Any self-reported survey data should
be used with caution with an understanding that error biases may potentially be
higher than other forms of data collection. A southeastern region weighted average

was calculated to compare with the given national average, and it was found that
the southeastern states have a smaller share (46.6 percent) of adult population
that consumed alcohol in the past month (of the survey) than the national average
(54.5 percent) (BRFSS, 2012). The Pearson Correlation Coefficient that was
calculated comparing the alcohol consumption by state to fatality rates by state was
-0.577, indicating that there is a moderate negative statistically significant
correlation between the two variables at a 95 percent confidence interval. It is of
importance to note that simply consuming an alcoholic beverage in the past month
is not in itself a risk-taking behavior, but rather the act of driving while intoxicated
would be considered a risk-taking behavior. Therefore the correlation coefficients
found in this section of the thesis may not be of much significance when referring to
fatality rate variations by risk-taking behavior characteristics. The same limitations
are present in the other types of drinking used in this thesis, as all the data relating
to alcohol consumption was retrieved from the same source. Binge drinking and
heavy drinking are again from self-reported survey collected data, and is found to
be less of an actual indicator of risk-taking behavior than originally hypothesized.
Binge drinking is defined by the BRFSS as more than five drinks at one time for a
male and more than four drinks at one time for a female. Another variable that was
compared to fatality rates is average share of the adult population that admitted to
binge drinking in the last 30 days. Binge drinking share also had a statistically
significant Pearson Correlation Coefficient at a value of -0.366, with a confidence
interval of 95 percent. While this is a statistically significant correlation, the
correlation is defined as moderate, not strong, and is less correlated than any
alcohol consumption is to fatality rates. The share of binge drinkers in the adult

population is less in the southeastern region than the national level (BRFSS, 2012).
This negative correlation is not what was expected, as the original hypothesis was
that as alcohol use, a potentially risky behavior, increases, fatality rates would also
increase. Yet as previously mentioned, the act of consuming an alcoholic beverage
is not necessarily a risky behavior in itself, but the risk associated with drinking
alcohol is introduced if driving occurs subsequent to the alcohol consumption. Given
the above mentioned limitations of the data in addition to the aggregate level that
the data was collected, the negative correlations are of little significance to this
thesis. Of possible greater significance, is the sales volume of alcohol, and the
correlations between alcohol sales and fatality rates. Gruenewald and Ponicki
(1995) report finding a positive correlation between alcohol sales and nighttime
fatal crashes using data from 38 states over a 12 year time period
(Gruenewald,P.J., Ponicki, W.R., 1995). McMillan and Lapham (2006) found a 42
percent increase in alcohol related crash fatalities on Sunday correlated to Sunday
packaged alcohol sales ban being lifted in New Mexico (McMillan,G.P., Lapham,S.,
2006).
4.3.4 Drug Use
Using the NSDUH given through the SAMHSA, drug use is categorized into
three categories in addition to five age groups, some of which are overlapping. The
categorization of drug use is defined as illicit drug use in the past month, marijuana
use in the past month, and illicit drugs other than marijuana in the past month. At
the national level it is theoretically sound to add the marijuana use and illicit drug
use other than marijuana to get total drug use, however because of the
methodology mentioned in section three of this thesis; it is not sound to do that
same iteration at the state level. The age groups that are included in the survey are
shown in Table 14.
Table 14 Age Groups of NSDUH
Age Group (years)
Represents
12 +
All respondents
12 - 17
Minor respondents
18 - 25
Young adult respondents
18 +
Adult respondents
26 +
Older adult respondents
Data source: NSDUH, 2012
For the all illicit drug use category, the Pearson Correlation Coefficient was
calculates to be inversely correlated (-0.53) in the 18 to 25 year old age range
when compared with total fatality rates. However, when the correlation to fatality
rates of only the 18 to 25 year old age group was calculated, all illicit drug use was
found to have a strong statistically significant correlation of 0.95 (NSDUH, 2012).
This is an indication that it is not sound to correlate independent characteristics of a
specific age group to a dependent characteristics that is inclusive of all age groups,
meaning the share of young adult illicit drug users is not directly correlated with the
overall fatality rate, but is strongly correlated to the fatality rate of young adults.
This presents a clearer representation of what one would expect, given drug use is
an inherently risky behavior that also causes an individual to behave in a risky
manner. The same trends are present in marijuana only use, and in illicit drugs
other than marijuana, however are not found to be of statistical significance at any

reasonable confidence interval (NSDUH, 2012). It should be noted that as
mentioned in the previous methodology, the sample size for the NSDUH is not
nearly the size of other similar population surveys, thus the results should be used
with caution.
4.3.5 Physical Health
The BRFSS reports shares of adults in body mass index (BMI) ranges from
underweight to obese, in addition to overall general health from poor to excellent.
For the purposes of this thesis, three physical health characteristics were chosen to
compare with fatality rates by state; obese BMI (30.0 or higher), excellent overall
health, and poor overall health. The national share of the adult population that is
classified as having an obese BMI is 29.4 percent, which is less than one percent
lower than the southeastern region average share of adult population with an obese
BMI (30 percent). Florida is the only state in the southeastern region that has a
lower share of obese adult population than the national average. The Pearson
Correlation Coefficient was calculated comparing the share of adult population that
is obese with the fatality rates by state was found to be 0.616, which is statistically
significant at a 95 percent confidence interval. It is worth noting again that
correlation coefficients do not indicate causation, but correlation, and it is
imperative that the two are not confused. When the correlation between general
health and obesity is calculated it was found that obesity has a statistically
significant strong direct correlation with poor health (0.714) and a statistically
significant strong inverse correlation with excellent health (-0.821). This is an
indication that as the share of adults that are obese increase, the share of adults

that are overall generally unhealthy increases, and the share of generally excellent
healthy population decreases. This is also an indication that both overall health and
obesity should not be included in a regression model to estimate fatality rates, as
they are more correlated with each other than they are correlated with fatality
rates.
In the case of overall health, Pearson Correlation Coefficients were calculated
between excellent overall health and fatality rates, between poor overall health and
fatality rates, and between excellent overall health and poor overall health. All
correlations were found to have moderate statistical significant correlations at a 95
percent confidence interval. Excellent overall health and fatality rates have a
moderate inverse correlation of -0.615. The healthier the population, the more
likely they are to survive a collision that an otherwise unhealthy person may not
have survived. Just as intuitive, the correlation between overall poor health and
fatality rates is a direct correlation of 0.666. If an unhealthy person is involved in a
traffic collision, their chances of survival is less than that of a healthy person. For
completeness, the overall poor health and overall excellent health were also
compared, and were found to have a strong inverse statistically significant
correlation of -0.771, indicating that they should not both be used in a regression
model to estimate the fatality rates by state.
4.3.6 Mental Health
Mental health was another area of exploration for the study of this thesis, in
the idea that decreased levels of cognitive mental capabilities may be indicative of

increased probability of behaving in risky manners. While the theoretical
relationship between risk-taking behavior increases with increased mental illness
made sense, especially throughout the literature review, where studies revealed a
higher propensity for risky sexual behavior among those with decreased mental
cognitive capabilities, the data in this thesis found no statistical significance in a
relationship between mental disabilities and fatality rates at a state level, with the
slight exception of one age group in one mental illness variable. The mental illness
variables that were explored were again from the NSDUH data; serious mental
illness in the past year, any mental illness in the past year, at least one major
depressive episode in the past year, and thoughts of suicide in the past year. In
general the southeastern region was fairly close to the national level in all mental
health characteristics. The only characteristic that was found to be slightly
statistically significant with fatality rates at the state level was the 26 and older age
group of serious mental illness in the past year, with a Pearson Correlation
Coefficient of 0.326. In order to be statistically significant at the 95 percent
confidence interval the Pearson Correlation Coefficient must have a magnitude
greater than or equal to 0.3.
4.3.7 Educational Attainment
Two categories of educational attainment were explored for comparison
between educational levels and fatality rates. Both categories were defined by the
U.S. Census Bureau as population 25 and older who has a high school diploma or
equivalent, and population 25 and older with a Bachelor’s degree or higher. The
Pearson Correlation Coefficient calculated was the highest between the shares of

population over 25 with a Bachelor’s degree or higher and fatality rates, at a value
of -0.742, indicating a strong inverse statistically significant correlation at a 95
percent confidence interval. This is an expected correlation, because in general, as
a person’s education level increases, their self-worth also increases, and their
propensity to partake in risky behavior that may jeopardize their hard work in
obtaining their education is greatly reduced. There is also a statistically significant
inverse correlation of -0.345 between the shares of population that obtained their
high school diploma or equivalent, however that correlation is not as strong as the
higher education correlation. When compared to share of the population below the
poverty level , the share of population who obtained their high school diploma is
greatly inversely correlated (-0.774). This means that as the share of population
that has completed high school increases, the share of population below poverty
level decreases, which is an expected relationship. The last educational correlation
coefficient that was calculated was the correlation between the share of population
who completed their high school education, and the share of population that
obtained a Bachelor’s degree or higher. This direct correlation was statistically
significant at a value of 0.407. With all the correlation coefficients taken into
consideration, it was concluded that the characteristic that should be included in the
regression model to estimate fatality rates is the share of population with a
Bachelor’s degree or higher at the age of 25.
4.4 Other Demographics Used for Regression
In order to have as reduce the unobserved or random component accounted
for in the error term of a regression model, a couple other characteristics aside

from the risk-taking characteristics being tested are included in the model.
Characteristics that are known to affect the fatality rates, from previously reviewed
literature, should be included so that the risk-taking characteristics are not being
misrepresented in the fatality rate estimation. Transportation safety is a complex
problem with numerous interconnected variables all having some type of
contribution overall. Unfortunately, it is unrealistic to include every influencing
factor in a thesis to estimate approximate fatality rates given the variation of
independent variable characteristics by geography. This thesis used characteristics
known to affect transportation safety in conjunction with several risk-taking
characteristics to estimate the amount of the risk-taking characteristics have on the
overall fatality rate at a state level. The demographic characteristics will also help to
estimate more accurate marginal effect coefficients to the risk-taking characteristics
in the linear regression model. For this model, the demographic characteristics
included are share of the population born in state of residence, and unemployed
share of population by state.
The share of population born in state of residence seems to be a moderately
decent indicator of the rate of unfamiliar drivers on the roadway network. This is
not implying that because you move to another state you are always an unfamiliar
driver, however, visitors from the state of origin will be unfamiliar drivers, and the
larger the share of residents born out of their state of residence, the larger the
share of friends and family that will visit the current state of residence. Inversely if
an individual lives in the state they were born in, the chances of them being
unfamiliar of the roadway network decreases. Familiarity of the roadway network
includes, but is not limited to, knowing where crosswalks and rail crossings are

located, knowing posted speed limits, school zones, senior zones, etc. and which
exit to take off the interstate. The share of unemployed population is considered as
one of the descriptive independent variables because the unemployed population
generally drives much less than the share of the population that is employed. The
reduction in travel contributes to the overall reduction in fatality rates because if an
individual is not traveling, their chances of being fatally injured while traveling are
significantly decreased via simple exposure rates. A report produced through the
NHTSA in 2010 revealed that the Metropolitan Statistical Areas with the highest
increase in unemployment between 2007 and 2008 also experienced the largest
decrease in fatalities, and the Metropolitan Statistical Areas with the smallest
increase in unemployment rates experienced the smallest decline in fatalities during
the same time period, citing great reductions in crashes involving young drivers,
multiple vehicle crashes and crashes which occurred on the weekends when most
discretionary driving occurs (NHTSA, 2010).
Other studies such as “The Effects of Mandatory Seat Belt Laws on Driving
Behavior and Traffic Fatalities,” by Cohen and Einav used independent descriptive
characteristics such as median income, mean age, share of black and Hispanic
population, rural density, violent crimes, speed limit, and fuel tax to explore the
differences in fatality rates by geography. “Gasoline Prices and Motor Vehicle
Fatalities,” by Grabowski and Morrisey used gasoline prices, license revocation, seat
belt laws, speed limit, unemployment rate, and income per capita to estimate
fatality rates by state. The results of the estimation are often dependent on the
geography the data is aggregated to. According to Clark and Avery (2010) due to
aggregation bias “it is incorrect to assume that relationships existing at one level of

analysis will necessarily demonstrate the same strength at another level’ (Clark and
Avery, 2010). For instance a variable that is known to have significant correlation at
a Census Tract aggregate level may not display the same significance or even the
same direction of relationship at a state level. Some other characteristics that are
commonly used as independent variables to describe a dependent variable of
fatality rates, but were not used in the regression analysis of this thesis include:
race, income, traffic density, property crimes, fuel taxes, fuel consumption, average
speed, vehicle expenditures, speed limit laws, gross national product, retail sales,
etc. Several of these mentioned independent variables are inter-correlated,
meaning it would not be meaningful nor correct to include all listed variables in one
regression analysis. As mentioned previously, safety is a complex problem with
multifaceted interrelated solutions which are not obvious nor easily solved, which is
why fatalities still occur on the roadway network.
4.5 Linear Regression
It is of extreme importance to note that the linear regression formed for this
thesis was formed at an aggregate state level. Aggregate level data is not ideal, as
it is not as accurate nor is it always as representative as disaggregate data. For
instance the average credit score of a specific city, Phoenix, Arizona is 737;
however the average credit score for the state of Arizona is only 640, indicating
that if an average state credit score is used to represent each city, the average
credit score for the city of Phoenix would be greatly underestimated.

Unfortunately, for the variables being used for consideration in this thesis, such as
credit score, smoking population, educational attainment, etc., consistent
disaggregate data is not available. Aggregate data has the potential to have
aggregation bias, where the correlations may appear to be statistically significant at
an aggregate level but not at a disaggregate level, or the regression analysis may
indicate a significantly different relationship between the dependent and
independent variables than would be apparent if the data were evaluated at a
disaggregate level (Clark and Avery, 2010). With the understanding that the
risktaking characteristics are at an aggregate state level, all calculations and
conclusions should be used with caution.
There are always unknowns present in regression analyses, some are known
unknowns and some are unapparent unknowns. In this thesis there are several
characteristics which were not considered because the scope of this thesis was
focused on risk-taking behaviors, and could not reasonably consider every impactful
possible characteristic. Some unknowns which are known to affect fatality rates
which were not considered in this thesis include types of vehicles driven, travel
speeds, state traffic laws, emergency response capabilities, weather, topography,
intersection density, time of day which the crash occurs, driving under the
influence, rural and urban share of crashes, etc. The error term in the regression
model attempts to account for all the characteristics which were not explored.
An estimated regression model of fatality rate as a function of average credit
score, share of population over 25 with bachelor’s degree or higher, share of
population with overall poor health, share of population who reports always using a
seat belt, share of population born in state of residency, and unemployed share of
population is shown in Equation 8.
Equation 8
where = fatality rate
= average credit score
= share of population over 25 with bachelor’s degree or higher
= share of population with overall poor health
= share of population that reports always using a seat belt
= share of population born in state of residency
= unemployed share of population
= error term to account for unknowns.
When all data was entered and calculated, the coefficients were determined and
shown in Equation 9.
Equation 9
where the terms represent the same variables as indicated in Equation 8.
It is important to understand that the above calculated linear regression
equation is using a limited number of variables, and as mentioned previously,
safety, specifically fatality rates, are extremely complex and impossible to
accurately measure with a limited number independent variables. The correlations,
both known and unknown, make this problem too complex to solve with one linear
regression equation. This thesis is an attempt at using the best available data to
distinguish the amount of effect risk-taking independent variables have on fatality
rates while also accounting for some demographic independent variables which are
known to effect fatality rates but are not too strongly correlated to the risk-taking
variables being used.

The sign of the coefficient of each independent variable determines whether
or not the dependent variable is directly or inversely related. If the sign of the
coefficient of the independent variable is positive, then the independent variable is
directly related to the dependent variable, meaning as the independent variable
increases the dependent variable also increases marginally at a proportion equal to
the magnitude of the coefficient, given all other variables are held constant. For
instance, for each percent share increase of the adult population with poor health,
the fatality rate of that geography should experience an increase of 0.079, given all
other independent variables remain the same. Contrarily, if the sign of the
independent variable is negative then the independent variable and the dependent
variable have an inverse relationship, meaning as the independent variable
increases, the dependent variable should decrease proportionately at the magnitude
of the independent variable coefficient given all other characteristics remain the
same. For instance, for each percent share increase of the population over 25 years
of age that obtains a bachelor’s degree or higher, the fatality rate should decrease
0.018; given all other independent variables remain constant.
It is also important to mention the error term which is present in the
regression model. The error term helps to explain the variability in fatality rates
when all independent characteristics are equal. Error terms are present in all
regression models and are assumed to represent a normal distribution with a mean
value of zero. The error term is considered the random or unobserved component in
the regression analysis. Once the regression analysis is estimated, the error term is
no longer included and the effects of the variables that are not included in the
model, or the unobserved characteristics, are captured in the constant term. Table
15 displays the parameter estimates, standard error of the estimate, and t statistic
for each of the explanatory variables, along with goodness of fit measures.
Table 15 Linear Regression Variable Estimates and Goodness of Fit Measures
Explanatory variable
Parameter
estimate
Standard
error (S.E.)
of the
estimate
t
statistic
Credit Score
-0.007
0.003
-2.169
≥25 yrs with Bachelor’s or higher
-0.018
0.006
-3.206
Overall Poor Health
0.079
0.024
3.264
Seat Belt Use
-0.005
0.004
-1.370
Residents born in state
-0.005
0.002
-2.702
Unemployed
-0.046
0.015
-3.140
Goodness of fit measures:
Regression Sums of Squares (SSR)
3.381
Residual Sums of Squares (SSE)
1.107
Total Sums of Squares (SST)
4.488
R2
0.753
Adjusted R2
0.721
Number of cases
52
Credit score was calculated to have an inverse effect on fatality rates at the
aggregate state level. This result was expected given the previously performed
literature review which revealed that as a person’s fiscal responsibility increases,
their credit score also increases. This increased credit score and increased fiscal
responsibility is accompanied by a decreased likelihood of risk-taking behavior. As

an individual’s likelihood of risk-taking behavior in financial matters decreases, their
likelihood of driving in a risky manner should also decrease. In addition to driving in
a safer manner, a fiscally responsible person is also more likely to keep their
vehicle properly maintained, such as getting regularly scheduled oil changes,
replacing tires prior to balding, replacing brake-pads at regular intervals, etc. This
regularly scheduled proper maintenance will reduce the likelihood of vehicle failure,
and thus reduces the chances of a collision due to vehicle failure. While fatality
rates are inclusive of all person types such as drivers, passengers, and pedestrians,
etc. decreasing the propensity of risk-taking behavior would have a positive effect
on all roadway network users.
The share of population with a Bachelor’s degree or higher was calculated to
have an inverse effect on fatality rates at the aggregate state level. This result was
expected given the previously performed literature review which revealed that as an
individual’s education levels increase their understanding of consequences which
accompany their actions also increases. Accompanying a better understanding of
consequences for actions is a reduced likelihood of driving while intoxicated,
distracted, at unsafe speeds, or without a seat belt. In addition, people with higher
education levels are more likely exhibit healthy behaviors such as eating a healthy
diet, exercising, refraining from smoking, all of which are examples of decreased
risk-taking behaviors which also lead to increased life expectancy.
The share of population with overall poor health was calculated to have a
direct relationship with fatality rates at the aggregate state level. This result was
expected given the previous literature review which assumes general health to be
related to chronic diseases, healthy behaviors, and access to preventative

healthcare services. Overall poor health can be caused by several factors which are
also considered to be risk-taking behaviors such as eating an unhealthy diet, lack of
exercise, being overweight, and smoking. Thus as risk taking behavior increases,
the chance of being classified as overall unhealthy also increases. This supports the
original hypothesis that as risk-taking behaviors increase, fatality rates also
increase.
The share of population which always wears a seat belt while driving was
calculated to have an inverse relationship with fatality rates at an aggregate state
level. Seat belt use, or rather lack of seat belt use is considered a risk-taking
behavior which is inherently different than the other risk-taking behaviors being
examined in this thesis. Seat belt use has been proven to reduce the severity of a
motor vehicle crash when used properly, and is the only risk-taking behavior
analyzed which has a direct effect on the injury severity of a vehicular crash. When
considering the other risk-taking characteristics which were examined in the
regression analysis, changing the proportionate share of population would not have
a direct effect on fatality rates. For instance, increasing the average credit score of
an individual does not inherently make them behave in a less risky manner thus
would not directly cause them to drive more carefully. Unlike the other risk-taking
characteristics reviewed however, increasing the share of the population that always
wears their seat belt can directly impact the fatality rates by reducing the injury
severity of collisions which occur.
The last two independent variables presented in the regression model were
not risk-taking characteristics, instead were demographic characteristics used to
help explain the variation in fatality rates. The share of population born in state of

residency was calculated to have an inverse correlation to the fatality rate by state.
This is an intuitive relationship because as previously stated, if a person resides in
the state in which they were born they are less likely to be unfamiliar drivers on the
roadway network. As the share of unfamiliar drivers on the roadway network
decreases, the variation in speed on that network should also decrease, and a
reduction in variation of speed is associated with a lower chance of collision
occurrence. In addition, a person born in their state of residence will likely know the
location of high risk of collision areas such as crosswalks, rail at-grade crossings,
etc. Finally, the share of unemployed population was calculated to an inverse
relationship to fatality rates by state. This is an intuitive correlation because an
unemployed individual will travel less than an employed individual, thus reducing
their exposure risk. Trip reduction of the unemployed population would not only be
due to less home-based work trips, but the lack of income associated with
unemployment would likely also lead to a reduction in all types of trips. This
reduction in trips equates to a decreased exposure rate, thus reducing the chances
of being involved in a fatal collision. This increased unemployment has shown to
lead to decreased crashes involving young drivers, multiple vehicle crashes, and
weekend crashes, all leading to reduced fatalities (NHTSA, 2010).
CHAPTER 5:
CONCLUSIONS

Fatality rates in each of the eight states in the southeastern region of the
U.S. have consistently been higher than the national average fatality rate in terms
of fatalities per VMT, and fatalities per population. As of 2012, three of the eight
southeastern states were ranked in the top ten of overall fatalities per capita in the
nation. Safety is an incredibly complex problem affecting every aspect of the
transportation sector. Each of the influencing characteristics associated with the
safety of a transportation network are interconnected in such a complicated way
which make a complete unanimous solution an impossible feat. With the complete
understanding that no one solution is going to have the ability of eliminating all
transportation fatalities which occur on the network, hypotheses are made to try to
understand why some regions have higher fatality rates than other regions. While
the southeastern region does have socio-economic and socio-demographic traits
such as higher levels of poverty, higher share of elderly population, higher minority
shares of population, and more vulnerable road users, which partially help to
estimate why fatality rates are higher in this region of the nation, this thesis
focused mostly non-conventional risk-taking characteristics as explanatory
variables. Many risk-taking characteristics were found to have significant
correlations to conventional characteristics used in previous literature to estimate
fatality rates at specific levels of geography, such as median income and share of
population with a Bachelor’s degree or higher. When two independent variables
exhibit strong correlations, using both the correlated independent variables would
not be of sound logic, and thus for the purposes of this thesis, median income was
replaced with share of population with a Bachelor’s degree or higher.

The hypothesis tested implies that if a person behaves in a risky manner in
economic and health aspects of their life, risk is likely present is several aspects of
their life, therefore that person is also expected to drive in a risky manner, and
delay maintenance of their vehicle which, would in turn equate to more collisions
and higher fatality rates. This is under the assumption that if a person displays
risktaking characteristics of any type, that person likely behaves in a risky manner
in other aspects of their life. This assumption of risk-taking behavior is used as a
great starting point to help explain variation in fatality rates in specific regions of
the nation where risk-taking behaviors and fatality rates are both higher than
national averages.
A breadth of risk-taking characteristics such as credit score, educational
attainment, seat belt use, tobacco, alcohol and drug use, obesity, and overall
health, were shown to have statistically significant bivariate correlations with
fatality rates, as shown in Table A1 in the appendix. Four risk-taking characteristics
were found to influence fatality rates at an integrated level when a linear regression
model was formed; average credit score, educational attainment, overall health,
and seat belt use. While one of the mentioned risk-taking characteristics -
propensity to use a seat belt - is directly related to fatality rates, the other
risktaking behaviors are indirectly related to fatality rates, such as credit score,
educational attainment, and overall health.
Seat belt use has been shown to reduce the injury severity of a vehicular
passenger when involved in a collision; therefore increasing the share of seat belt
using population in a region such as the southeastern region of the U.S. would
directly impact the fatality rates of the region. In the context of other risk-taking

characteristics considered in this thesis, the relationship with fatality rates is not
necessarily causal. Correlation is not causation; two variables that are statistically
significantly correlated does not imply that changing one variable would cause a
change in the other variable. For example, increasing the share of population that
has a higher education may not directly lead to a reduction of fatality rates unless
that increase in educational attainment is coupled with a reduction in overall
sensation-seeking or risk-taking behavior. The correlation between fatality rates and
educational attainment is due to the typical characteristics of an individual with a
higher educational attainment, not the education level itself. As stated in the
literature review of this thesis, a person with a higher education level is more likely
to consider the consequences of their actions, have a higher self-worth, and have a
higher household income, all of which are characteristics associated with decreased
levels of risk-taking behavior. Increasing education levels in itself will not
necessarily increase these traits associated with decreased risk-taking, however it is
likely that as education levels increase awareness would also increase, decreasing
overall risk0-taking behavior. Still, all interpretations of the calculated regression
model from chapter four must be considered with caution.
Credit score is similar to educational attainment, in that there is not a direct
relationship between credit score and fatality rates, however the literature review
revealed that credit score increases are associated with likelihood of vehicle
maintenance and cautious driving habits, which have the ability to influence fatality
rates. As revealed in the literature review, a consumer who is prudent in their own
financial matters is also expected to be more prudent in vehicle maintenance and
display more cautious driving habits. It is not the increased credit score in itself that

reduces the fatality rates; it is the underlying responsible characteristic of an
individual that leads to a high credit score and reduced propensity to engage in risk-
taking behavior. This is an indication that simply increasing the average credit score
in a particular geography would not reduce the fatality rates in that geography,
unless the increased credit score is coupled with changes in the typical traits that
reduce risk-taking behavior.
Poor overall health is perhaps the most indirect characteristic which is related
to risk-taking behaviors and correlated to fatality rates, at least at a state level
geography. The literature review revealed that overall poor health is related to
chronic diseases, unhealthy behaviors and lack of preventative health-care services
such as regular check-ups, with the most common factors to overall poor health
being specific risk-taking behaviors such as smoking, consuming an unhealthy diet,
lack of exercise, and being overweight. Again, the distinction between correlation
and causation must be fully understood. This correlation between poor overall
health and fatality rates does not indicate that simply increasing the overall health
levels of a population would directly decrease vehicular fatality rates. The increased
health of the overall population would necessarily be coupled with an overall
decrease of risk-taking behaviors in order to have any impact on the fatality rates in
the region. For instance, just because someone eats a healthy diet and exercises,
thus increasing their overall health, does not mean that individual will not drive in a
risky manner, nor does this indicate that person is more likely to survive a collision
than a person who eats an unhealthy diet and does not exercise, however a healthy
individual may be more attentive or less fatigued while driving, thus reducing their
risk of collision while driving. The correlation should be interpreted as the likelihood

of risk-taking behaviors increases, the chances of classification of overall poor
health also increases, in addition, the probability of collision increases due to the
increased risk-taking behavior.
It is important to reiterate that the linear regression model was formed using
state level aggregate data, and therefore the chance of aggregate bias is
introduced. Unfortunately, there is not much risk-taking characteristic disaggregate
data available for analyses, leading to the requirement of using data aggregated to
the state level. When data is aggregated at the state level in the U.S. the data
points are then limited to 52 cases when the District of Columbia and the national
average are also included as data points. To improve the usefulness of the linear
regression model, more data points and more variables could be introduced;
however this adds a level of difficulty beyond the scope of study for this thesis.
To reduce the driving related risk-taking behavior, measures which have
previously been shown to be effective include making laws more comprehensive by
changing non-existent or secondary laws to primary laws which are inclusive of all
roadway users, coupled with increased enforcement, and increased perception of
enforcement. Increasing enforcement is most effective when media is also
emphasizing the enforcement to increase the perception of enforcement as well.
The increased enforcement should be placed on policies such as safety belt and
helmet use, booster-seat use, speeding, and distracted driving such as texting while
driving. Reducing these directly related risk-taking characteristics should produce
the greatest associated decrease in fatality rates in the southeastern U.S.
In addition to reducing the risk-taking behaviors that have a direct effect on
fatality rates, efforts should also be made to implement education and counseling to

the share of population that is known to behave in risky manners. Education and
counseling will not eliminate the share of population that behaves in a risky manner
while driving; however it may help to reduce the risk-taking behaviors of those
individuals who are not aware of the risk-taking characteristics they possess. Some
individuals display risk-taking characteristics because they don’t care, nor do they
desire to reduce their amount of risk-taking behaviors. The implementation of
counseling and educating services will not have much impact on individuals who do
not want to change their habits, however there is likely a share of the population
who displays risk-taking characteristics because they do not know any better, or are
unaware of the consequences that may accompany their behavior. For the share of
population who would behave in a less risky manner if they knew better, education
and counseling could be beneficial. The counseling and education referred to should
emphasize the reduction of risk-taking characteristics directly related to fatality
rates such as increasing safety belt and helmet use, reducing distractions while
driving, reducing driving under the influence, reducing speed, and driving
defensively rather than aggressively. If education and counseling implementations
reduce overall risk-taking behavior, then the fatality rates would also decrease,
increasing the total safety of the roadway network as a whole.
Additional efforts focusing on the addition of more variables could
significantly enhance the usefulness of the efforts put forth in this thesis. Increasing
the number of variables included in the regression analysis would help to reduce the
error associated with the unobserved characteristics and increase the usefulness of
the results by including more suggestions of policy implications. In addition to
increasing the number of variables, decreasing the size of data aggregation would

help to reduce aggregation bias and possibly infer better focused policy
implications. In addition, remediation actions are easier and less expensive at small
geographies, rather than at the state level, and the aggregation of the data used in
the analyses of this thesis does not allow for small geography associations and the
subsequent targeted actions.
Carrying out the analyses in this thesis on sub-segments of the overall
fatality data may enhance the usefulness of the linear regression estimation. For
instance, comparing the independent risk-taking variables with only alcohol related
fatalities may help to clarify the characteristics specifically associated to driving
while intoxicated. Similarly sub segments such as urban versus rural or freeway
versus non-freeway may help to distinguish what types of areas are most influenced
by specific characteristics within specific designs. For instance most freeways are
relatively constant over geographies, therefore the variation of fatality rates on
freeways by state may show a better indication of the influence specific risk-taking
traits of the population in that area have on fatality rates. A further exploration of
daytime versus nighttime and vulnerable versus vehicular road user fatalities may
help to distinguish why the southeastern states have a higher pedestrian fatality
rate when compared to the other states in the U.S. and what risk-taking
characteristics are playing a significant role in the fatality rate differences.
This thesis can be used as a starting point for additional analysis that can
assist states in moving closer to a zero traffic fatality goal. As previously mentioned,
safety is a complex problem and numerous strategies will need to be deployed
together to find solutions which work to reduce fatalities in each area. Reducing
risk-taking behaviors -traits that are disproportionately common in the southeastern

states - of drivers, pedestrians and bicyclists are a component of the myriad of
activities to improve the transportation vehicles, infrastructure, enforcement and
education efforts directed toward improving travel safety.

