


1
THE ROLE OF THE LOWER TRAPEZIUS MUSCLE IN SHOULDER IMPINGEMENT
AND SCAPULAR DYSKINESIS
Chapter 1: Introduction
The complex anatomy and biomechanics of the human shoulder are subjected to
significant stress during activities such as throwing baseballs, swimming, handling overhead
materials, and other repetitive overhead actions. The term "shoulder impingement," introduced by
Neer (1972), provides insight into the etiology, pathology, and treatment of this prevalent shoulder
condition. Historically, patients with shoulder impingements have been treated using subacromial
decompression. However, Tibone et al. (1985) showed that the success rate of overhead athletes
is only 43%, and only 22% of throwing athletes return to their sport. As a result, alternative causes
of pain in overhead throwers are being explored.
Jobe et al. (1989) proposed the concept of instability as a precursor to secondary impacts,
hypothesizing that shoulder instability in overhead throwing athletes can lead to secondary
subachromial impacts. Later, Jobe (1996) described the "internal expanse," which occurs between
the articular side of the posterior rotator cuff and the posterior glenoid labrum when the shoulder
is in abduction and external rotation.
This condition is particularly challenging in overhead athletes because the throwing
movement involves speed, repetition, and high skill (Wilk et al., 2009; Conte, Requa, & Garrick,
2001). The force acting on the shoulder during the throw includes an angular velocity of about
7250°/s and a distractive force equal to or exceeding the body weight (Wilk et al., 2009). The
glenohumeral joint is the most frequently injured joint in professional baseball pitchers and other
overhead athletes (Sorensen & Jorgensen, 2000).

2
To avoid shoulder impingements and other pathologies, the shoulder complex in overhead
athletes must maintain high muscle strength, adequate joint mobility, and sufficient stability (Wilk
et al., 2009; Sorensen & Jorgensen, 2000; Heyworth & Williams, 2009; Forthomme, Crielaard, &
Croisier, 2008). When pathology appears, it usually manifests as reduced throwing performance,
strength deficit, reduced range of motion, joint laxity, and pain (Wilk et al., 2009; Forthomme,
Crielaard, & Croisier, 2008).
Doctors must understand the underlying cause of abnormal shoulder dynamics in overhead
athletes with impact to develop an effective treatment plan and ensure long-term health. Current
research focuses on shoulder and scapular kinematics, muscle activity, static posture, and
evidence-based exercise prescriptions to address deficits. However, there is still uncertainty
regarding the relationship between kinematics and the mechanisms underlying shoulder
impingement syndrome (SIS) in athletes above the head.
The purpose of this paper is to review the literature on pathomechanics, electromyography
activity (EMG), and clinical considerations related to shoulder impingement in overhead athletes.
IMPORTANCE OF A DISSERTATION
The purpose of this project is to analyze the electromyography activity (EMG) of the
lower trapezius during therapeutic exercises commonly used for individuals with shoulder
impingement and to evaluate the role of the lower trapezius in scapular dyskinesis. Understanding
the specific EMG profile of these exercises is essential for rehabilitation professionals to choose
the right exercise dosage and movement pattern for effective muscle rehabilitation.
Furthermore, data from the first study in this dissertation were used to identify therapeutic

3
exercises with the highest potential to activate and fatigue the lower trapezius. By inducing fatigue
in the lower trapezius, this study aims to examine the impact of fatigue on scapular discinesis and
its role in increasing the risk of injury. These insights are essential for preventing severe shoulder
injuries, improving overall shoulder health, and improving rehabilitation strategies.
The findings from this study may provide valuable information about the mechanisms
underlying shoulder impacts and injuries, contributing to improved prevention and treatment
approaches.

4
CHAPTER 2: LITERATURE REVIEW
This review will begin by discussing the history, incidents, and epidemiology of shoulder
impingements in Section 1.0, which will also address the relevant anatomy and pathophysiology
of normal and pathological shoulders. The next section, 2.0, will discuss the specific and general
limitations of EMG analysis. The following section, 3.0, will discuss shoulder and scapular
movements, muscle activation, and muscle timing in healthy, impacted shoulders. Finally, section
4.0 will discuss the clinical implications and rehabilitation effects on overhead athletes with
shoulder impingements.
2.1 HISTORY, INCIDENTS, AND EPIDEMIOLOGY OF SHOULDER IMPACT
Shoulder impingements account for 44%-65% of all cases of shoulder pain (Neer, 1972; Van
der Windt, Koes, de Jong, & Bouter, 1995) and is commonly seen in overhead athletes due to the
biomechanics and repetitive nature of overhead movements in sports. Generally, the most affected
types of sports activities include throwing athletes, racquet sports, gymnastics, swimming, and
volleyball (Kirchhoff & Imhoff, 2010).
Subachromial impingement syndrome (SIS), a commonly seen diagnosis in overhead athletes
coming to rehabilitation, is characterized by shoulder pain that is exacerbated by arm elevation or
overhead activity. Usually the rotator cuff, the long head of the biceps tendon, and/or the
subacromial bursa "bumps" under the acromion in the subacromial space causing pain and
dysfunction (Ludewig & Cook, 2000; Lukaseiwicz, McClure, Michener, Pratt, & Sennett, 1999;
Michener, Walsworth, & Burnet, 2004; Nyberg, Jonsson, & Sundelin, 2010). Factors proposed
to contribute to SIS can be classified as intrinsic or extrinsic and then further classified, based on
the cause of the problem, into primary, secondary, or posterior impacts (Nyberg, Jonsson, &
Sundelin, 2010).

5
2.1.1 Anatomy and pathophysiology of the relevant shoulder complex
When discussing the relevant anatomy in shoulder impingement, it is important to have an
understanding of the glenohumeral muscles and the scapula-thoracic scapula, subacromial space
(SAS), and the soft tissues that can become "impingements" in the shoulder. The main muscles of
the shoulder complex include the rotator cuff (RTC) (supraspinatus, infraspinatus, teres minor, and
subscapularus), stabilizer scacouple (rhombus major and minor, upper trapezius , lower trapezius ,
middle trapezius and serratus anterior), deltoid, and accessory muscles (latisimmus dorsi, biceps
brachii, coracobrachialis, pectoralis major, pectoralis minor). The shoulder also contains many
bursa, one of which is clinically significant in overhead athletes with an impact called a
subacromial bursae. The subacromial bursa is located between the deltoid muscle and the
glenohumeral joint capsule and extends between the acromion and the supraspinatus muscle.
Often, with repeated overhead activity, the subacromial bursae can become inflamed leading to a
reduction in the subacromial space (Wilk, Reinold, & Andrews, 2009). The supraspinatus tendon
is located under the subachromial bursae and inserts on the superior aspect of the larger humerus
tubercle and is the most susceptible to RTC muscle impact. The infraspinatus tendon inserts the
posterior-inferior supraspinatus tendon in the larger tuberculum and can be struck by the anterior
acromion during shoulder movement.
The SAS is an area 10mm below the achromial arch in the shoulder (Petersson & Redlund-
Johnell, 1984) and contains many soft tissue structures including tendons, ligaments, and bursae
(Figure 1). These structures can become compressed, or "bumped", in the SAS causing pain due
to excessive migration of the humerus head, scapulas discinesis, muscle weakness, and bone
abnormalities. Any subtle deviation (1-2 mm) from the normal drop in SAS can contribute to
impact and pain (Allmann, et al., 1997; Michener, McClure, and Karduna,

6
The researchers have compared painful and normal shoulder static radiographs at various positions
of the glenohumeral range of motion, and their findings include: 1) humerus head excursions
greater than 1.5 mm are associated with shoulder pathology (Poppen & Walker, 1976),
2) patients with impingement showed superior humerus head migration of 1mm (Deutsch,
Altchek, Schwartz, Otis, & Warren, 1996), 3) patients with RTC tears (with and without pain)
showed superior humerus head migration with elevation increase between 60° – 150° compared
to normal control (Yamaguchi, et al., 2000), and 4) in all studies, it was shown that SAS decrease
was associated with pathology and pain.
To maintain the SAS, the scapula rotates upwards which will lift the lateral acromion and
prevent impact, but the SAS will show a decrease of 3mm-3.9mm in non-pathological subjects
at 30-120 degrees of abduction (Ludewig & Cook, 2000; Graichen, et al., 1999).
The posterior slope of the scapula also prevents the impact of the RTC tendon by lifting
the anterior acromion and maintaining the SAS.
Shoulder impingement, is believed to contribute to the development of RTC disease
(Ludewig & Braman, 2011; Van der Windt, Koes, de Jong, & Bouter, 1995), is the most commonly
diagnosed shoulder disorder in primary health care and although its prevalence is reported, the
diagnostic criteria and etiology of SIS are debatable (Ludewig & Braman, 2011). SIS is a soft
tissue encroachment in the SAS due to the narrowing of this space (Figure 1, B), and after an
impact occurs, the shoulder soft tissue can and can develop through 3 stages of lesions (usually
and overhead athletes progress through these stages more quickly) (Wilk, Reinold, Andrews,
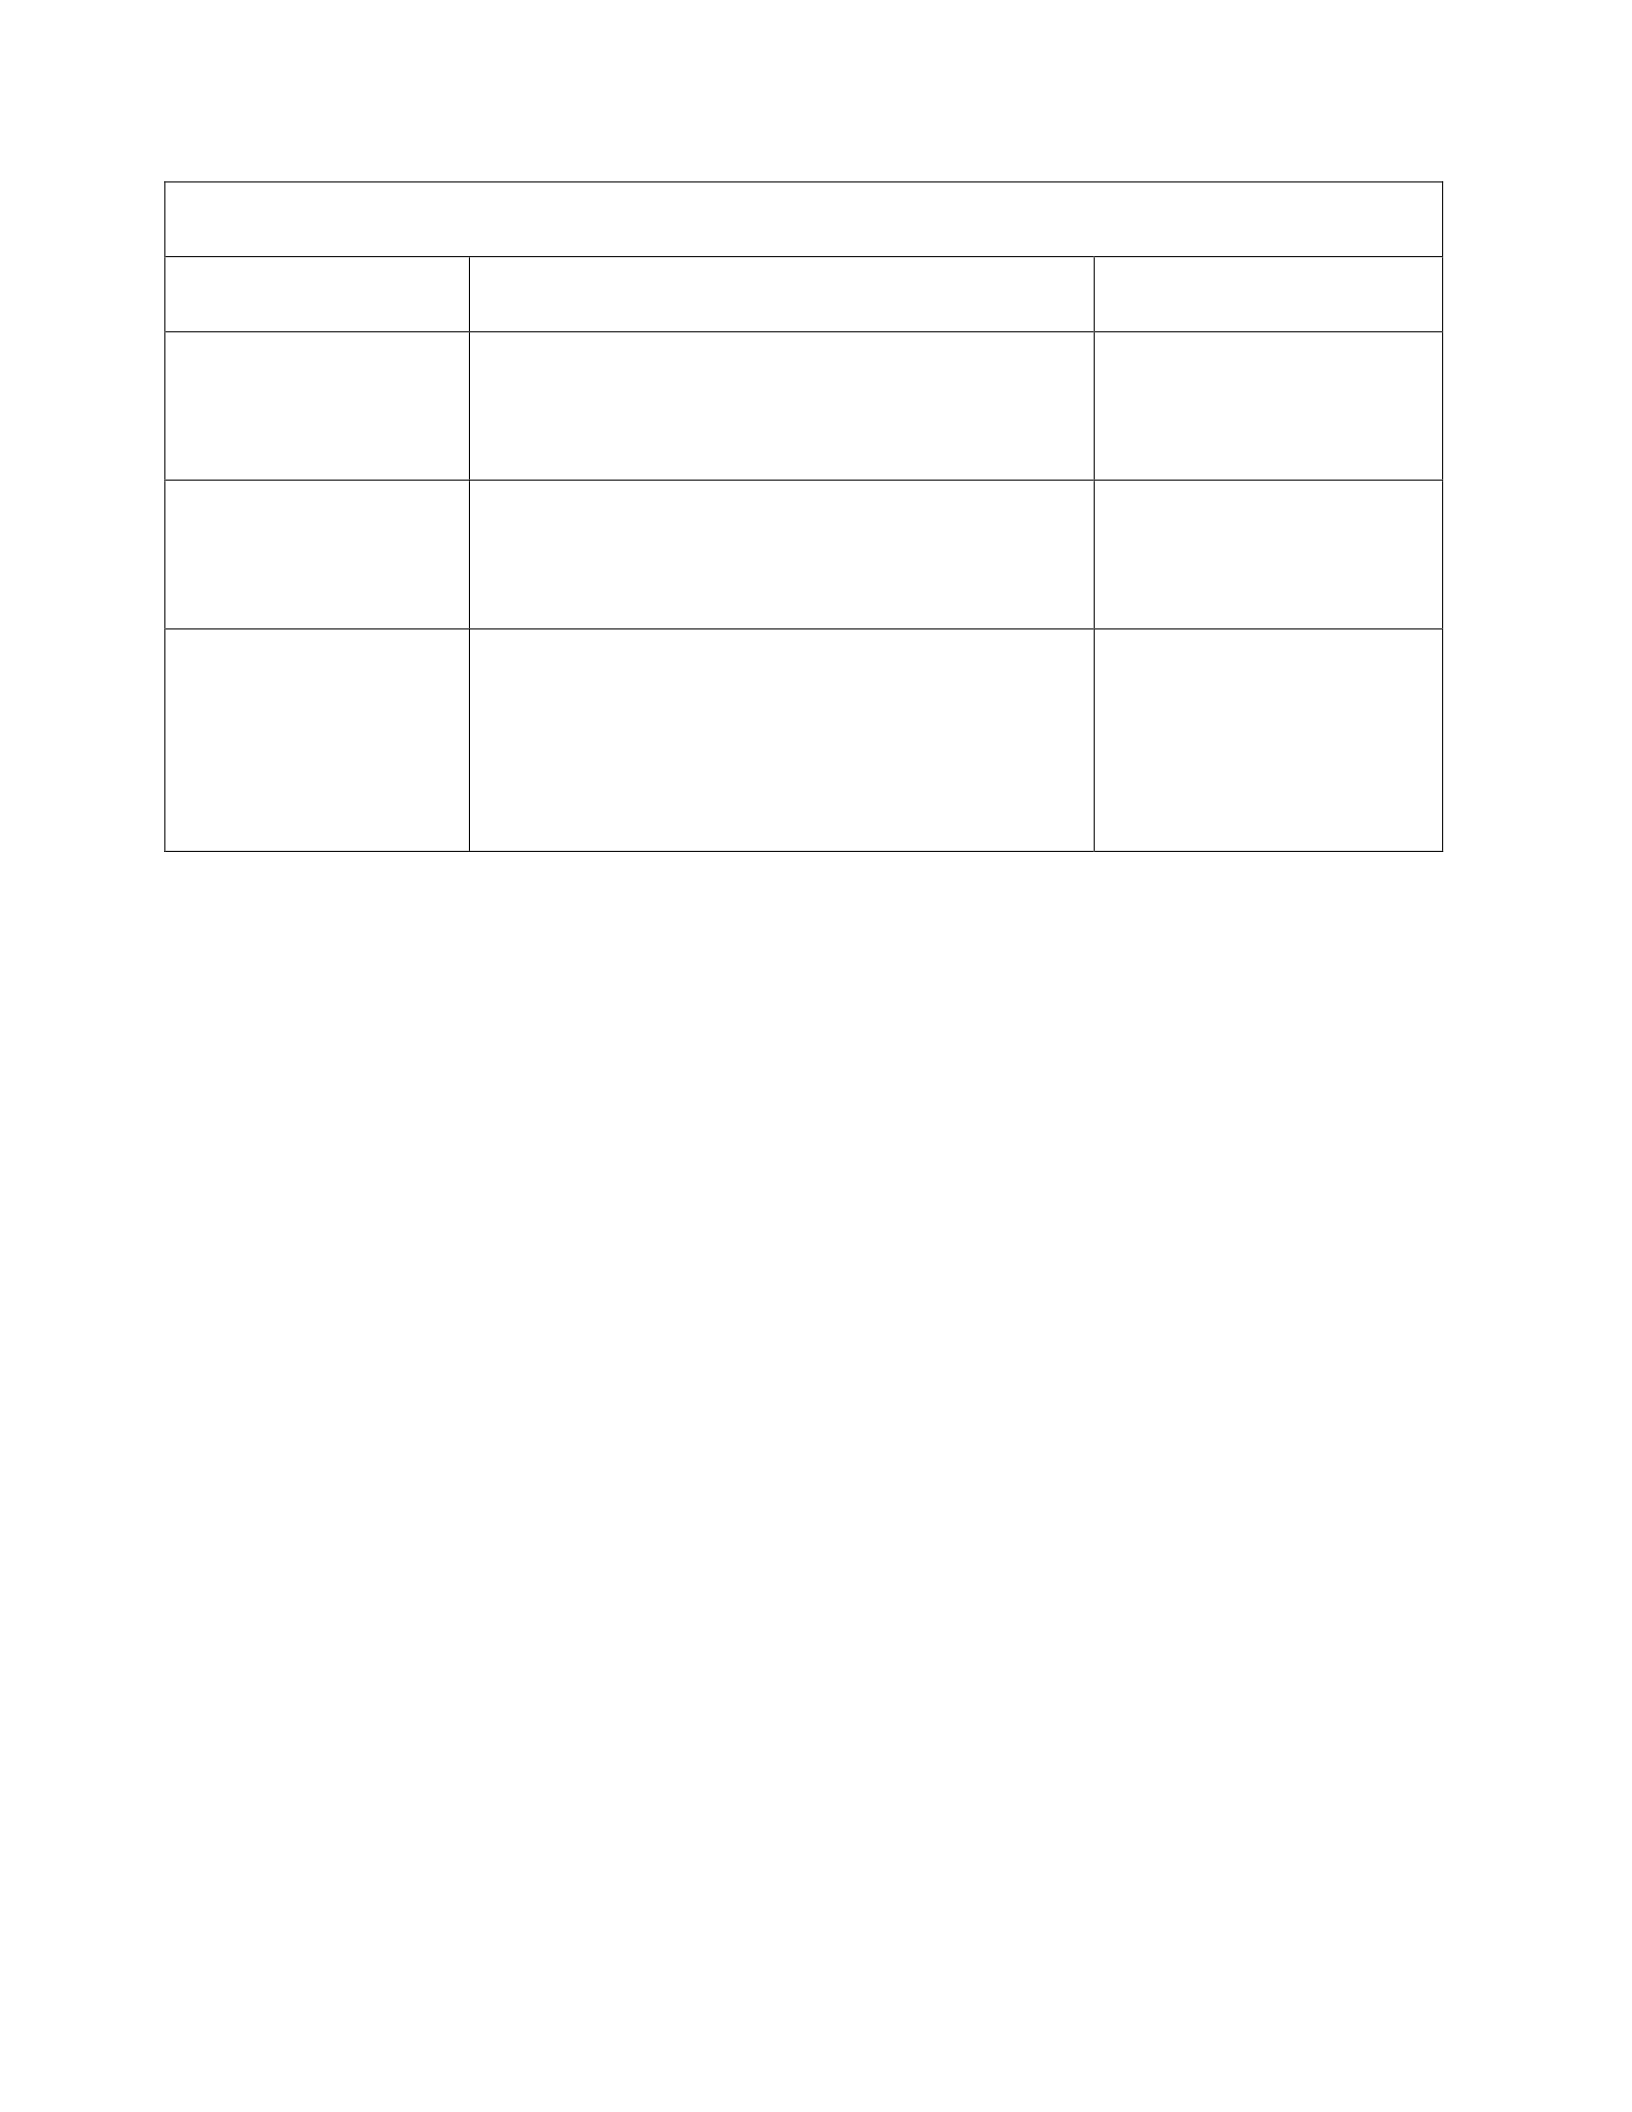
2009). Neer described (Neer, 1983) three stages of lesions (Table 1) and the higher the stage, the
more difficult it is to respond to conservative treatments.
7
Table 1: Better classification of lesions in impingement syndrome
Stage
Characteristic
Typical Age of Patients
Phase I
edema and bleeding of the bursa and cuff,
reversible with conservative treatment
< 25 years
Phase II
irreversible changes, such as fibrosis and
rotator cuff tendinitis
25-40 years
Phase III
by partial or complete tearing of the rotator
cuff and/or biceps and acromion tendons
and/or joint pathology of the AC
>40 years
SIS can be separated into two main mechanistic theories and two less classical forms of impact.
The two main theories include Neer's impingement theory (Neer, 1972) which focuses on extrinsic
mechanisms (primary impingement) and the second theory focuses on intrinsic mechanisms
(secondary impingement). Less classic forms of shoulder impact include internal impact and
coracoid impact.
Primary shoulder impingement results from mechanical abrasion and compression of the
RTC tendon, subacromial bursa, or long head of the biceps tendon under the anterior subsurface
of the acromion, coracoacromial ligament, or subsurface of the acromioclavicular joint during arm
elevation (Neer, 1972). This type of impact is usually seen in people over 40 years old and is
usually caused by degeneration. Scapular discinesis has been observed in this population and led
to superior translation of the head of the humerus, which further degrades SAS (Lukaseiwicz,
McClure, Michener, Pratt, & Sennett, 1999; Ludewig & Cook, 2000; de Witte, et al., 2011).
In some studies, the correlation between the achromial form (Bigliani classification type
II or type III) (Figure 1) (Bigliani, Morrison, & April, 1986) and SIS has been observed and it has

8
been assumed that crooked acromions are pre-existing anatomical variations or traction spurs
caused by repeated superior translations of the humerus or by tendinopathy (Nordt, Garretson, &
Plotkin, 1999; Hirano, Ide, & Takagi, 2002; Jacobson, et al., 1995; Morrison, 1987). This
subjective classification has been applied to the study of achromia using several types of imaging
and has shown poor to moderate intra-observer reliability and inter-observer repetition.
Figure 1: Bigliani classification of acromion forms based on the appearance of the supraspinatus outlet
on a radiograph (Bigliani, Morrison, & April, 1986; Wilk, Reinold, & Andrews, 2009).
Other studies concluded that there was no relationship between SIS and achromial shapes,
or discussed the difficulty of using subacromial shapes as a judgment tool (Bright, Torpey, Magid,
Codd, & McFarland, 1997; Burkhead & Burkhart, 1995). Generally, partial RTC tearing is
referred to as a consequence of SIS and it is expected that this tear will occur on the side of the
RTC bursal if it "hits" against the bent acromion. However, most partial RTC tears occur either
intra-tendinous or on the articular side of the RTC (Wilk, Reinold, & Andrews, 2009). Despite
these differences, extrinsic mechanisms form the reason for the achromioplasty surgical
procedure, which is one of the most common surgical procedures performed on the shoulder (de
Witte, et al., 2011).
The second theory of shoulder impact is based on an intrinsic degenerative mechanism
and is known as secondary shoulder impact. Secondary shoulder impingement results from

9
intrinsic damage to the RTC tendon (most often the supraspinatus watershed zone) as a result of
overstress and ischemia. It is usually seen in overhead athletes from the age of 15-35 years and
is caused by problems with the muscles dynamics and instability of the shoulder or associated
scapula (de Witte, et al., 2011). Typically, this condition is enhanced by overuse, subacromial
inflammation, excess strain on the degenerative RTC tendon, or inadequate RTC function that
leads to an imbalance in joint stability and mobility, with the consequence of altered shoulder
kinematics (Yamaguchi, et al., 2000; Mayerhoefer, Breitenseher, Wurnig, & Roposch, 2009;
Uhthoff & Sano, 1997). Instability is generally classified as traumatic or atraumatic, as well as
by direction (anterior, posterior, inferior, or multidirectional) and number (grade I-grade III) of
instability (Wilk, Reinold, & Andrews, 2009). Instability in overhead athletes is usually caused
by repetitive microtrauma, which can contribute to secondary shoulder impingements (Ludewig
& Reynolds, 2009).
Recently, internal impacts have been identified and suspected to be caused by mechanical
friction and abrasion on the subsurface of the supraspinatus and infraspinatus against the anterior
or posterior glenoid glenoid rim or glenoid labrum.
This has been seen posteriorly in overhead athletes when the arm is abducted to 90 degrees
and rotated externally (Pappas, et al., 2006) and is usually accompanied by posterior shoulder
pain complaints during this late throw phase when the arm is in the final range of external rotation
(Myers, Laudner, Pasquale, Bradley, & Lephart, 2006). Posterior shoulder tightness (PST) and
glenohumeral internal rotation deficit (GIRD) have also been associated with internal
impingement by Burkhart and colleagues (Burkhart, Morgan, & Kibler, 2003). PST correction
through physical therapy has been shown to lead to resolution of internal impingement symptoms
(Tyler, Nicholas, Lee, Mullaney, & Mchugh, 2012).
Coracoid impingement is usually associated with anterior shoulder pain in the extreme

10
range of internal rotation of the glenohumeral (Jobe, Coen, & Screnar, 2000). This type of impact
is less often discussed but consists of subscapularis tendons collided between the coracoid process
and the lower tuberosity of the humerus (Ludewig & Braman, 2011).
Because the RTC muscles are involved in throwing and overhead activities, partial thickness
tears, full-thickness tears, and rotator cuff disease are seen in athletes above the head. When this
becomes a chronic condition, secondary impingement or internal impingement can result in
primary traction cuff disease (PTCD) or primary compression cuff disease (PCCD). PTCD,
hypothesized as a byproduct of internal impact, occurs during the slow phase of the throw in the
stable shoulder and is the result of a large repetitive eccentric load placed on the RTC when
attempting to slow down the arm resulting in partial subsurface tearing of the supraspinatus and
infraspinatus tendons (Andrews & Angelo, 1988; Wilk, et al., 2009). In contrast, PCCD occurs
on the bursal side of the RTC and results in partial thickness tearing of the RTC. It is hypothesized
that the process that causes the decrease in SIS increases the risk of this pathology and that this
is a byproduct of the imbalance and weakness of the RTC muscles especially during the slowing
phase of the throw (Andrews & Angelo, 1988). During the final cocking phase and the initial
acceleration of the throw, with the arm at maximum external rotation, the rotator cuff has the
potential to be an impact between the humerus head and a posterior-superior, internal or posterior
glenoid impact (Wilk, et al., 2009), and can cause articular or subsurface tearing of the RTC in
the athlete overhead.
In conclusion, RTC tear can be caused mainly by 3 mechanisms in overhead athletes
including internal impact, primary pull cuff disease (PTCD), or primary compression cuff disease
(PCCD) (Wilk, et al., 2009) and the causes of SIS are multifactorial and variable.

11
2.2 HISTORY, INCIDENTS, AND EPIDEMIOLOGY OF SCAPULA DISCINESIS
The scapula and its associated movements are important components that facilitate normal
functional movement in the shoulder complex, while maintaining the stability of the shoulder and
acting as a force transfer area (Kibler & McMullen, 2003). Assessing the movement and position
of the scapula is an important part of clinical examination (Wright, et. al., 2012) and identifying
the presence or absence of optimal movement to guide certain treatment options (Ludwig &
Reynolds, 2009). The literature lacks the ability to identify whether the altered position or
movement of the scapula is specific to shoulder pathology or if these changes are normal variations
(Wright, et al., 2012). Scapula movement disorders consist of premature, excessive, or
disrhythmic movements during an increase in active glenohumeral, a decrease in the upper
extremities or in bilateral comparisons (Ludwig & Reynolds, 2009; Wright, et al., 2012). Studies
have shown that the scapula rotates upwards (Ludwig & Reynolds, 2009), tilts backwards, and
rotates externally to clear the acromion from the humerus in forward elevation. Also, the scapula
synchronously rotates externally while tilting backwards to maintain the glenoid as a congruent
socket for the moving arm and maximize the kinematic concave compression of the sphere and
socket. The scapula is also dynamically stabilized in the retraction position during arm use to
maximize the activation and long tension relationship of all muscles derived from the scapula
(Ludwig & Reynolds, 2009). Finally, the scapula is a link in the kinetic chain of integrated
segmental movements that starts from the ground and ends at the hand (Kibler, Ludewig, McClure,
Michener, Bak, Sciascia, 2013). Due to the important but minimal stabilization of the scapula bone
by the clavicle through the acromioclavicular joint, dynamic muscular function is the primary
method by which the scapula is stabilized and deliberately moved to complete its role. Muscle
activation is coordinated in a pattern of special power pairs to allow for position stabilization and

12
control dynamic combined movements. Also, the scapula will help the achromial elevation to
increase the subacromial space for the cleaning of the underlying soft tissue (Ludwig & Reynolds,
2009; Wright, et al., 2012) and, for this reason, a change in the scapular position is important.
The clavicle exists to help maintain optimal scapular position during arm movements (Ludwig
& Reynolds, 2009). In this way, it acts as a support for the shoulder as it attaches the arm to the
axial skeleton through the acromioclavicular and sternoclavicular joints. An injury to one of the
static restraints can cause the scapula to become unstable, which in turn will negatively impact the
function of the arm (Kibler & Sciascia, 2010).
Previous research has found that changes in scapular position or movement are evident in 68%
to 100% of patients with shoulder disorders (Warner, Micheli, Arslanian, Kennedy, & Kennedy,
1992) resulting in compensatory movement in the distal segment. These movements begin to lead
to a decrease in dynamic control of the deceleration of the humeral head and lead to shoulder
pathology (Voight, Hardin, Blackburn, Tippett, & Canner, 1996; Wilk, Meister, & Andrews,
2002; McQuade, Dawson, & Smidt, 1998; Kibler & McMullen, 2003; Warner, Micheli, Arslanian,
Kennedy, & Kennedy, 1992; Nadler, 2004; Hutchinson & Ireland, 2003). For this reason, the
effects of scaular fatigue require more research.
Upward rotation of the scapular provides a stable base during overhead activities and previous
studies have examined the effects of fatigue on scapula movement and shoulder function (Suzuki,
Swanik, Bliven, Kelly, & Swanik, 2006; Birkelo, Padua, Guskiewicz, & Karas, 2003; Su,
Johnson, Gravely, & Karduna, 2004; Tsai, McClure, & Karduna, 2003; McQuade, Dawson, &
Smidt, 1998; Joshi, Thigpen, Bunn, Karas, & Padua, 2011; Tyler, Cuoco, Schachter, Thomas, &
McHugh, 2009; Noguchi, Chopp, Borgs, & Dickerson, 2013; Chopp, Fischer, & Dickerson, 2011;
Madsen, Bak, Jensen, & Welter, 2011). Previous studies have found no changes in the upward
scapula rotation due to fatigue in healthy individuals (Suzuki, Swanik, Bliven, Kelly, & Swanik,

13
2006) and healthy overhead athletes (Birkelo, Padua, Guskiewicz, & Karas, 2003; Su, Johnson,
Gravely, & Karduna, 2004). However, the results of this study should be interpreted with caution
and may not be applied to functional movement because one study (Suzuki, Swanik, Bliven,
Kelly, & Swanik, 2006) performed overhead sit-ups before and after fatigue with healthy college-
age men. Since the kinematics and dynamics of the overhead throw could not be seen while
sitting, the authors' results could not make comparisons with overhead athletes or pathological
populations because the participants were healthy. Also, since the scapula is thought to be
involved in the kinetic chain of overhead motion (Kibler, Ludewig, McClure, Michener, Bak, &
Sciascia, 2013), sitting will limit the movement of the scapula and limit the interpretation of the
resulting scapula motion.
Nonetheless, some researchers have identified a decrease in upward scaular rotation in healthy
subjects and subjects with shoulder pathology (Su, Johnson, Gravely, & Karduna, 2004; Warner,
Micheli, Arslanian, Kennedy, & Kennedy, 1992; Lukaseiwicz, McClure, Michener, Pratt, &
Sennett, 1999). In addition, after shoulder complex fatigue, significant changes in scapular
position (upward rotation decrease, posterior tilt, and external rotation) have been demonstrated
using exercises that induce scapular and glenohumeral muscle fatigue (Tsai, McClure, &
Karduna, 2003). However, previous research has focused on shoulder external rotational fatigue
and not on scapula muscle fatigue.
The lack of agreement in the findings is explained by the nature of the measurements used,
which differ between static and dynamic motion, as well as instrumentation. One explanation for
this difference involves the muscles being targeted for fatigue. For example, several studies have
examined shoulder complex fatigue due to functional activity (Birkelo, Padua, Guskiewicz, &
14
Karas, 2003; Su, Johnson, Gravely, & Karduna, 2004; Madsen, Bak, Jensen, & Welter, 2011)
while others have compared more isolated scapula muscle fatigue protocols (McQuade, Dawson,
& Smidt, 1998; Suzuki, Swanik, Bliven, Kelly, & Swanik, 2006; Tyler, Cuoco, Schachter,
Thomas, & McHugh, 2009; Chopp, Fischer, & Dickerson, 2011), and others have examined
shoulder complex fatigue (Tsai, McClure, & Karduna, 2003; Joshi, Thigpen, Bunn, Karas, &
Padua, 2011; Noguchi, Chopp, Borgs, & Dickerson, 2013; Madsen, Bak, Jensen, & Welter, 2011;
Chopp, Fischer, & Dickerson, 2011). Therefore, to date, no previous studies have specifically
targeted the lower trapezius muscle using therapeutic exercises with a maximum muscle
activation pattern.
2.2.1 Pathophysiology of scapula discinesis
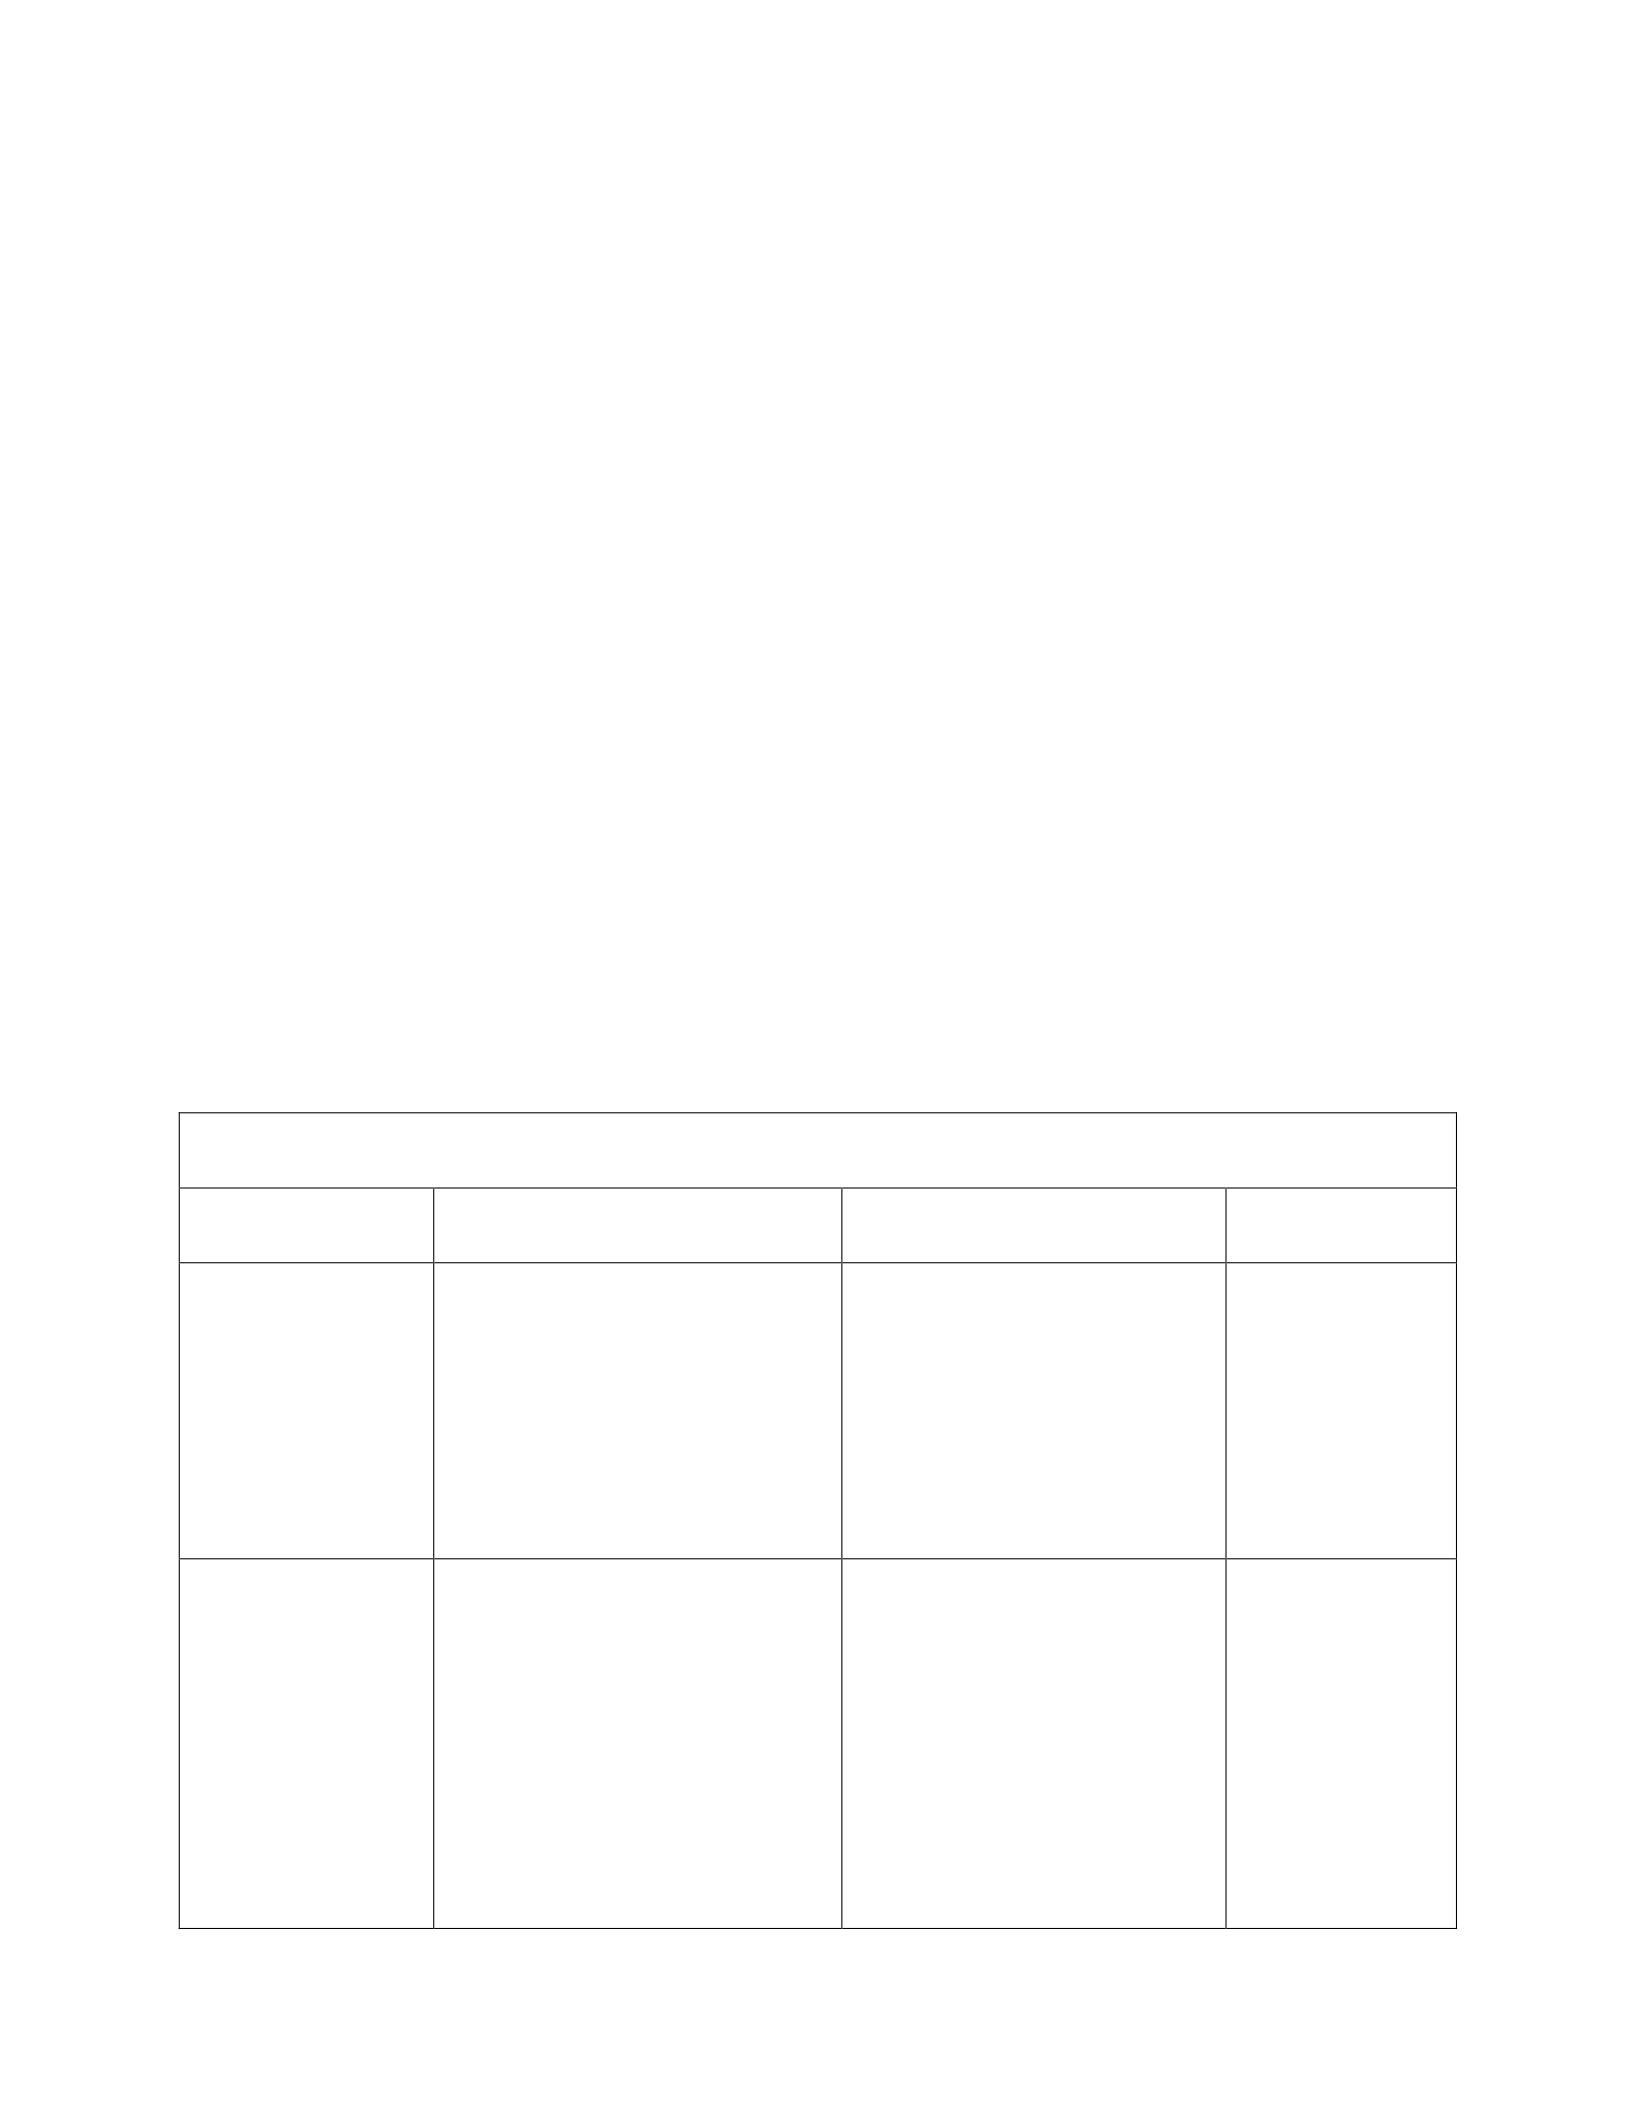
Abnormal movement and/or position of the scapula are collectively called "scapula wings",
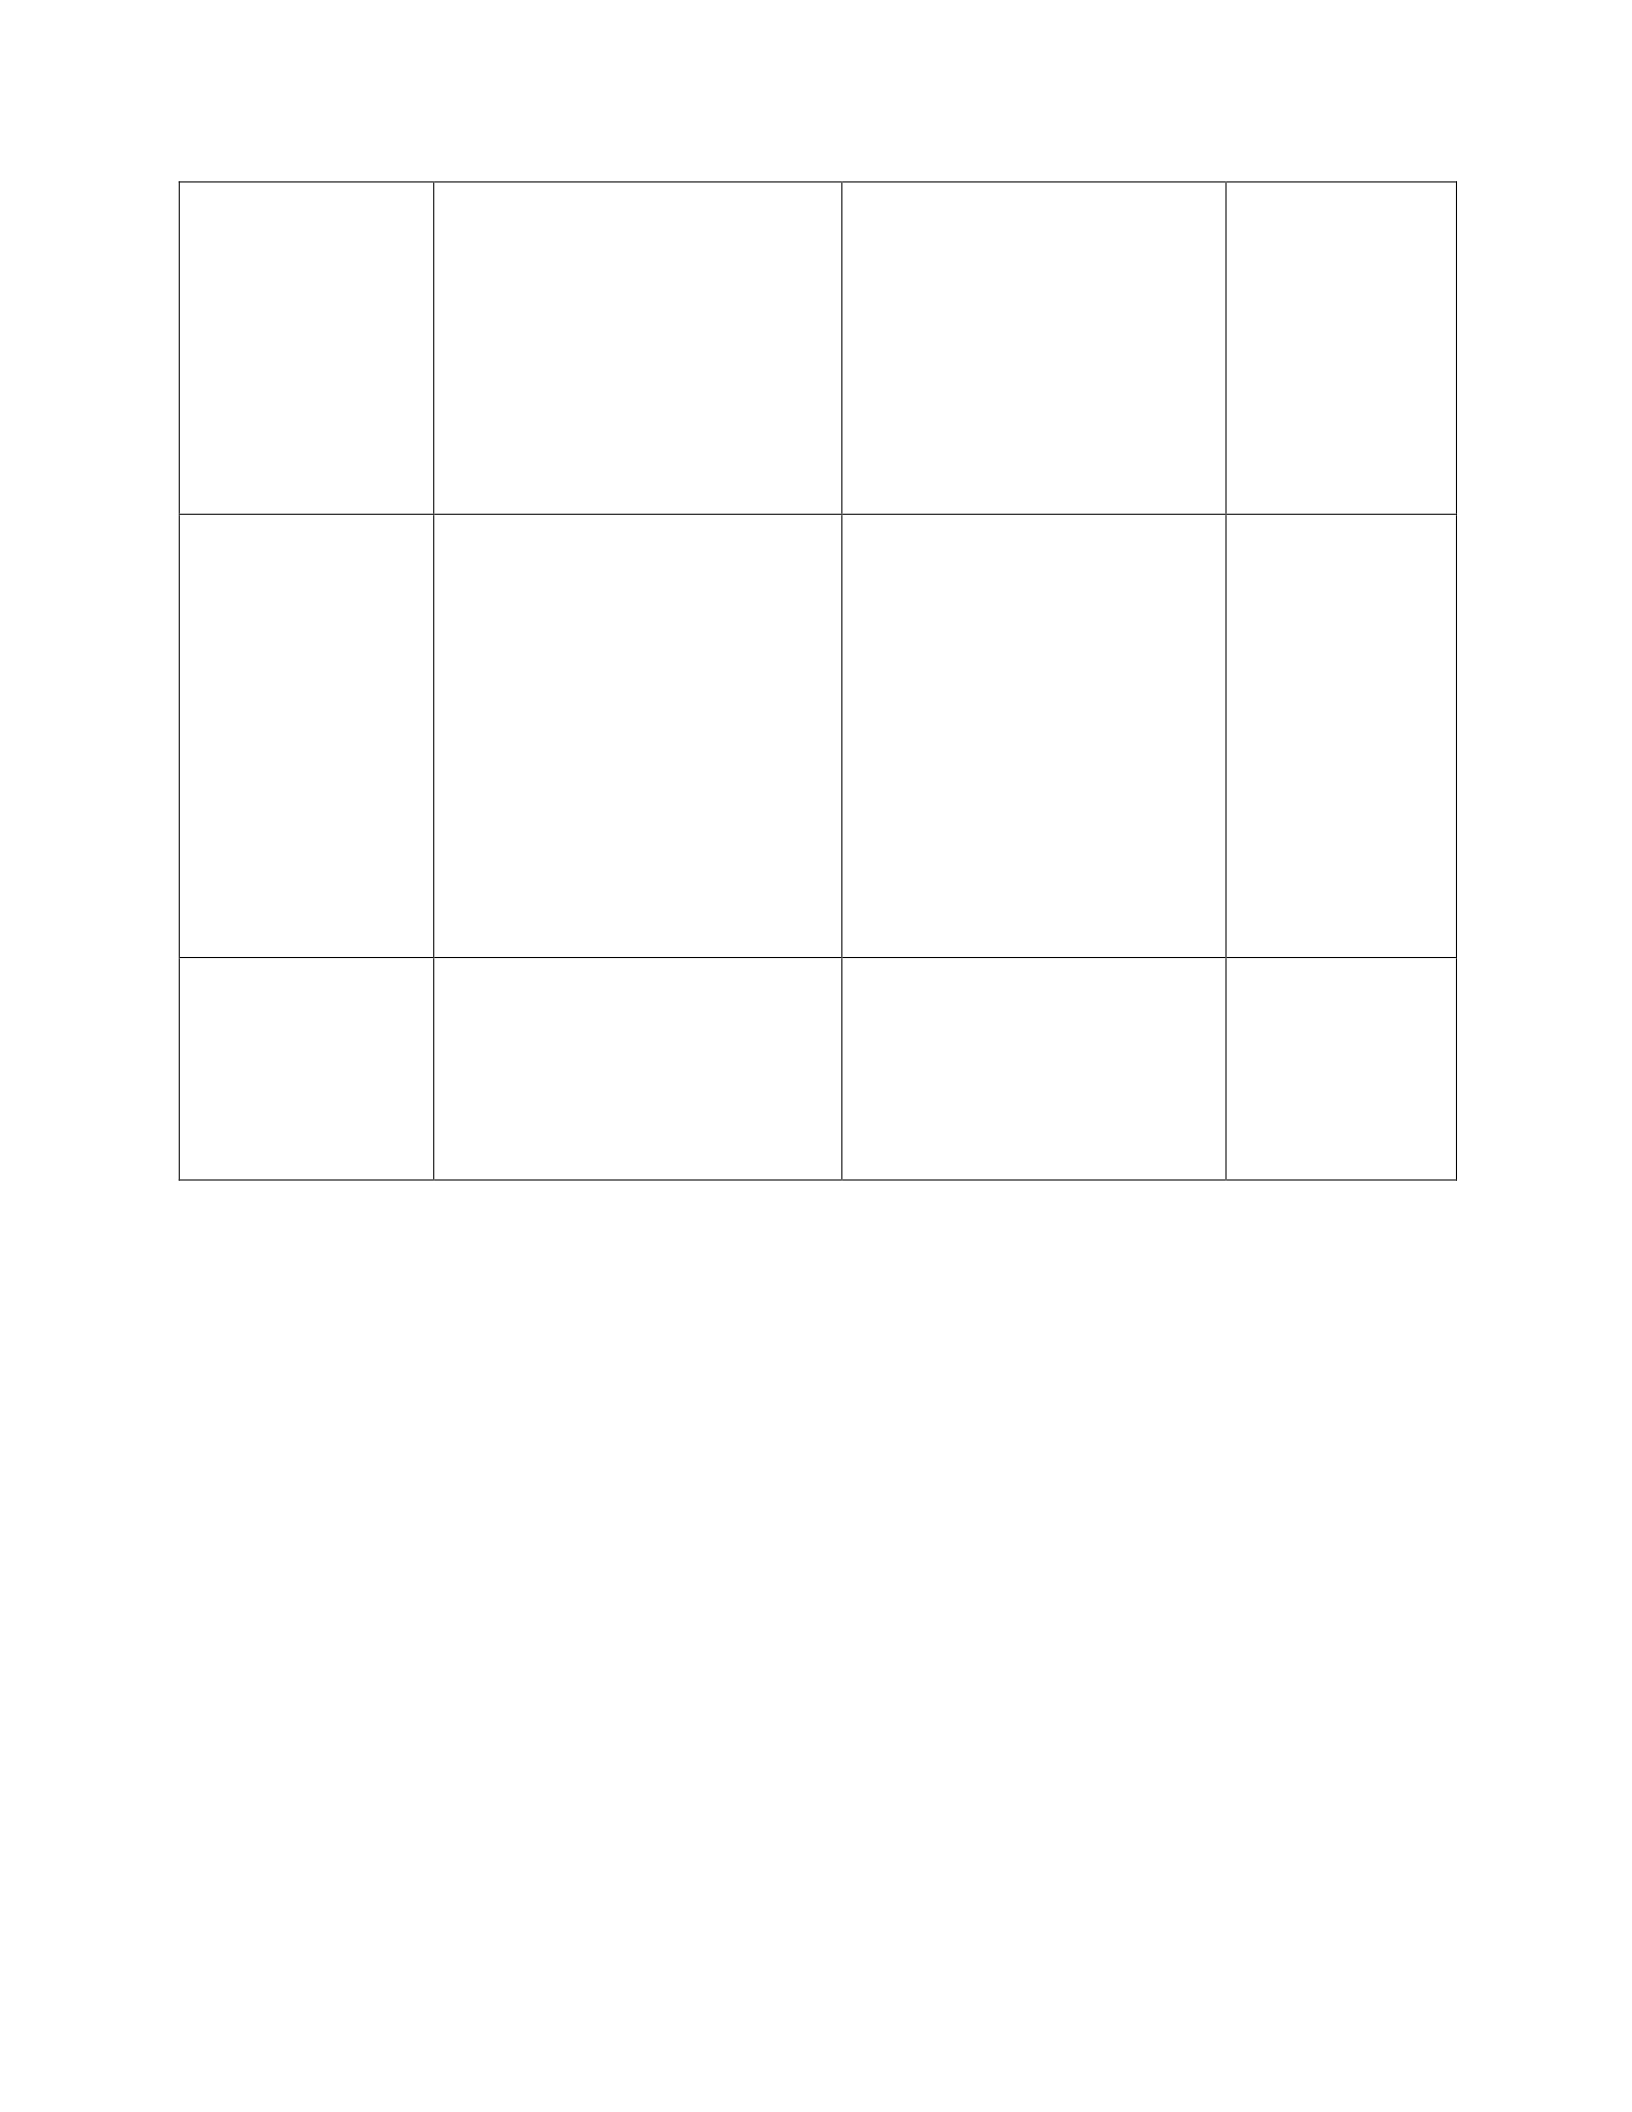
"scapula dyskinesia", "altered scapula resting position", and "scapula dyskinesis" (Table 2).
Table 2: Terminology of abnormal scapula motion
Term
Definition
Possible Causes
Static/Dynamic
Scapula wings
visual disorders
Advantages of the medial
border of the scapula
paralysis of the long thoracic
nerve
or obvious weakness of the
scapular muscles
both
Diskinesia
skapula
The loss of voluntary
movement has occurred only
scapular translations
(elevation/depression and
retraction/protraction) can be
adhesions, limited range of
motion, nerve paralysis
Dynamic
15
done voluntarily, whereas
scapular
Rotation is optional
dyskinesis
skapular
refers to dysfunctional scapula
movements
weakness/imbalance, nerve
injury and
acromioclavicular joint
injury, superior labral tear,
rotator cuff injury, clavicle
fracture, impact
Dynamic
Altered scapula
Resting position
Explaining static
Appearance of the scapula
Fractures, congenital
abnormalities, the scapula is
PAINFUL
Static

16
The most appropriate term to refer to the dysfunctional dynamic movement of the scapula is
the term scapular discinesis ('dys'—change, 'kinesis'—movement). When the arm is raised above
the head, generally accepted patterns of scapulothoracic movement are upward rotation, external
rotation, and posterior tilt of the scapula as well as clavicle elevation and retraction (Ludewig, et
al., 1996; McClure, et al., 2001). Of the 14 muscles attached to the scapula, the trapezius and the
anterior serratus play an important role in the production and control of scapulothoracic movement
(Ebaugh, et al., 2005; Inman, et al., 1944; Ludewig, et al., 1996). In addition, scapular dyskinesis
is reported to be more prominent because the arm is lowered from an overhead position and
individuals with shoulder pathology generally report more pain when lowering the arm (Kibler &
McMullen, 2003; Sharman, 2002).
Scapular discinesis has been identified by a group of experts as: (1) abnormal static scapula
position and/or dynamic scapular movement characterized by medial boundary protrusions; or (2)
inferior angular protrusion and/or early scapular elevation or shrugging of the arm elevation; and/or
(3) rapid downward rotation during arm drop (Kibler & Sciascia, 2010). Scapular discinesis is a
non-specific response to a painful condition in the shoulder rather than a specific response to a
specific glenohumeral pathology and altering the scapulohumeral rhythm. Scapular discinesis
occurs when the upper trapezius, middle trapezius, lower trapezius, anterior serratus, and
latissimus dorsi (stabilizing muscles) are unable to maintain typical scapula movement (Kibler &
Sciascia, 2010). Scapula discinesis is potentially dangerous when it results in increased anterior
tilt, downward rotation, and protraction, which redirects the acromion and reduces the width of
the subacromial space (Tsai, et al., 2003; Borstad, et al., 2009).
Changes in static (bone) stabilizers, muscle activation patterns, or scapula muscle strength
have contributed to scapula dyskinesis. Researchers have shown that injuries in

17
stabilizing the ligaments of the acromioclavicular joint can cause the scapula to shift in a
downward position, drag on, and rotate internally (Kibler & Sciascia, 2010). With displacement
of the scapula, significant functional consequences to the biomechanics of the shoulder occur
including the release of the scapulohumeral complex, the inability of the scapular stabilizing
muscles to maintain the proper position of the glenohumeral and acromiohumeral joints, and the
subsequent loss of strength and function of the rotator cuff (Joshi, Thigpen, Bunn, Karas, & Padua,
2011).
Scapular discinesis is associated with impact by altering the movement of the arm and the
position of the scapula at dynamic elevation, which is characterized by the loss of upward
achromial rotation, excessive internal rotation of the scapular, and excessive anterior tilt of the
scapular (Cools, Struyf, De Mey, Maenhout, Castelein, & Cagnie, 2013; Forthomme, Crielaard,
& Croisier, 2008). These related changes lead to a decrease in the subacromial space and increase
the risk of individual impacts.
Previous studies have shown changes in the activation sequence pattern and strength of
scapula-stabilizing muscles in individuals diagnosed with risk of impact and scapula dyskinesis
(Cools, Struyf, De Mey, Maenhout, Castelein, & Cagnie, 2013; Kibler & Sciascia, 2010). Each
scapula muscle makes a special contribution to the function of the scapula, but the lower trapezius
and anterior serratus seem to play a major role in stabilizing the scapula during arm movement.
Weakness, fatigue, or injury to any of these muscles can lead to impaired dynamic stability,
leading to abnormal kinematics and impingement symptoms. In a previous study (Madsen, Bak,
Jensen, & Welter, 2011), the authors showed an increased incidence of scapula scaninesis in pain-
free competitive overhead athletes during increased training and

18
Fatigue. The prevalence of scapula discinesis appears to increase with increased training to a
cumulative attendance of 82% in pain-free competitive overhead athletes.
A classification system, which aids in the clinical evaluation of scapula discinesis, has also
been reported in the literature (Kibler, Uhl, Maddux, Brooks, Zeller, & McMullen, 2002) and
modified to improve sensitivity (Uhl, Kibler, Gecewich, & Tripp, 2009). This method classifies
scapula discinesis based on the prominent part of the scapula and includes four types: 1) inferior
angular patterns (Type I), 2) medial boundary patterns (Type II), 3) superior boundary patterns
(Type III), and 4) normal patterns (Type IV). The examiner first predicted whether the individual
had scapula discinetic (yes/no method) and then classified the individual pattern type, which had
higher sensitivity (76%) and a positive predictive value (74%) than any other measure of clinical
discinetic (Uhl, Kibler, Gecewich, & Tripp, 2009).
Increased upper trapezius activity, upper trapezius activation imbalance/lower trapezius
activation, and decreased anterior serratus activity have been reported in patients with
impingement (Cools, Struyf, De Mey, Maenhout, Castelein, & Cagnie, 2013; Lawrence, Braman,
Laprade, & Ludewig, 2014). The authors have hypothesized that impact due to lack of acromial
elevation is caused by increased activity of the upper trapezius (shriveling maneuver) resulting in
a pattern of type III dyskinesis (upper medial border bulge) (Kibler & Sciascia, 2010). Often, the
activation of the lower trapezius is inhibited or delayed (Cools, Struyf, De Mey, Maenhout,
Castelein, & Cagnie, 2013), which results in a pattern of type III/type II dyskinesis (the entire
medial boundary advantage) and the stretch due to the loss of achromial elevation and posterior
slope (Kibler & Sciascia, 2010).
Scapular and kinematic positions affect the strength of the rotator cuff (Kibler, Ludewig,
McClure, Michener, Bak, & Sciascia, 2013) and previous studies (Kebaetse, McClure, & Pratt,
1999) have
19
Exhibits a 23% decrease in maximum rotator cuff strength due to excessive scapular protraction,
a posture often seen in individuals with scapula dyskinesis. Another study (Smith, Dietrich,
Kotajarvi, & Kaufman, 2006) showed that maximum rotator cuff strength was achieved with a
'neutral protraction/scapular retraction' position and excessive protraction/retraction position
showed a decrease in the rotator cuff abduction force.
Lastly, studies have shown (Kibler, Sciascia, & Dome, 2006) a 24% increase in supraspinatus
strength in the scapular retraction position in individuals with shoulder pain and an 11% increase
in individuals without shoulder pain. Clinically observable findings in scapula discinesis, the
dominance of medial scapula boundaries, are associated with the biomechanical position of internal
rotation and scapula protraction, which is a less than optimal basis for muscle strength (Kibler, &
Sciascia, 2010).
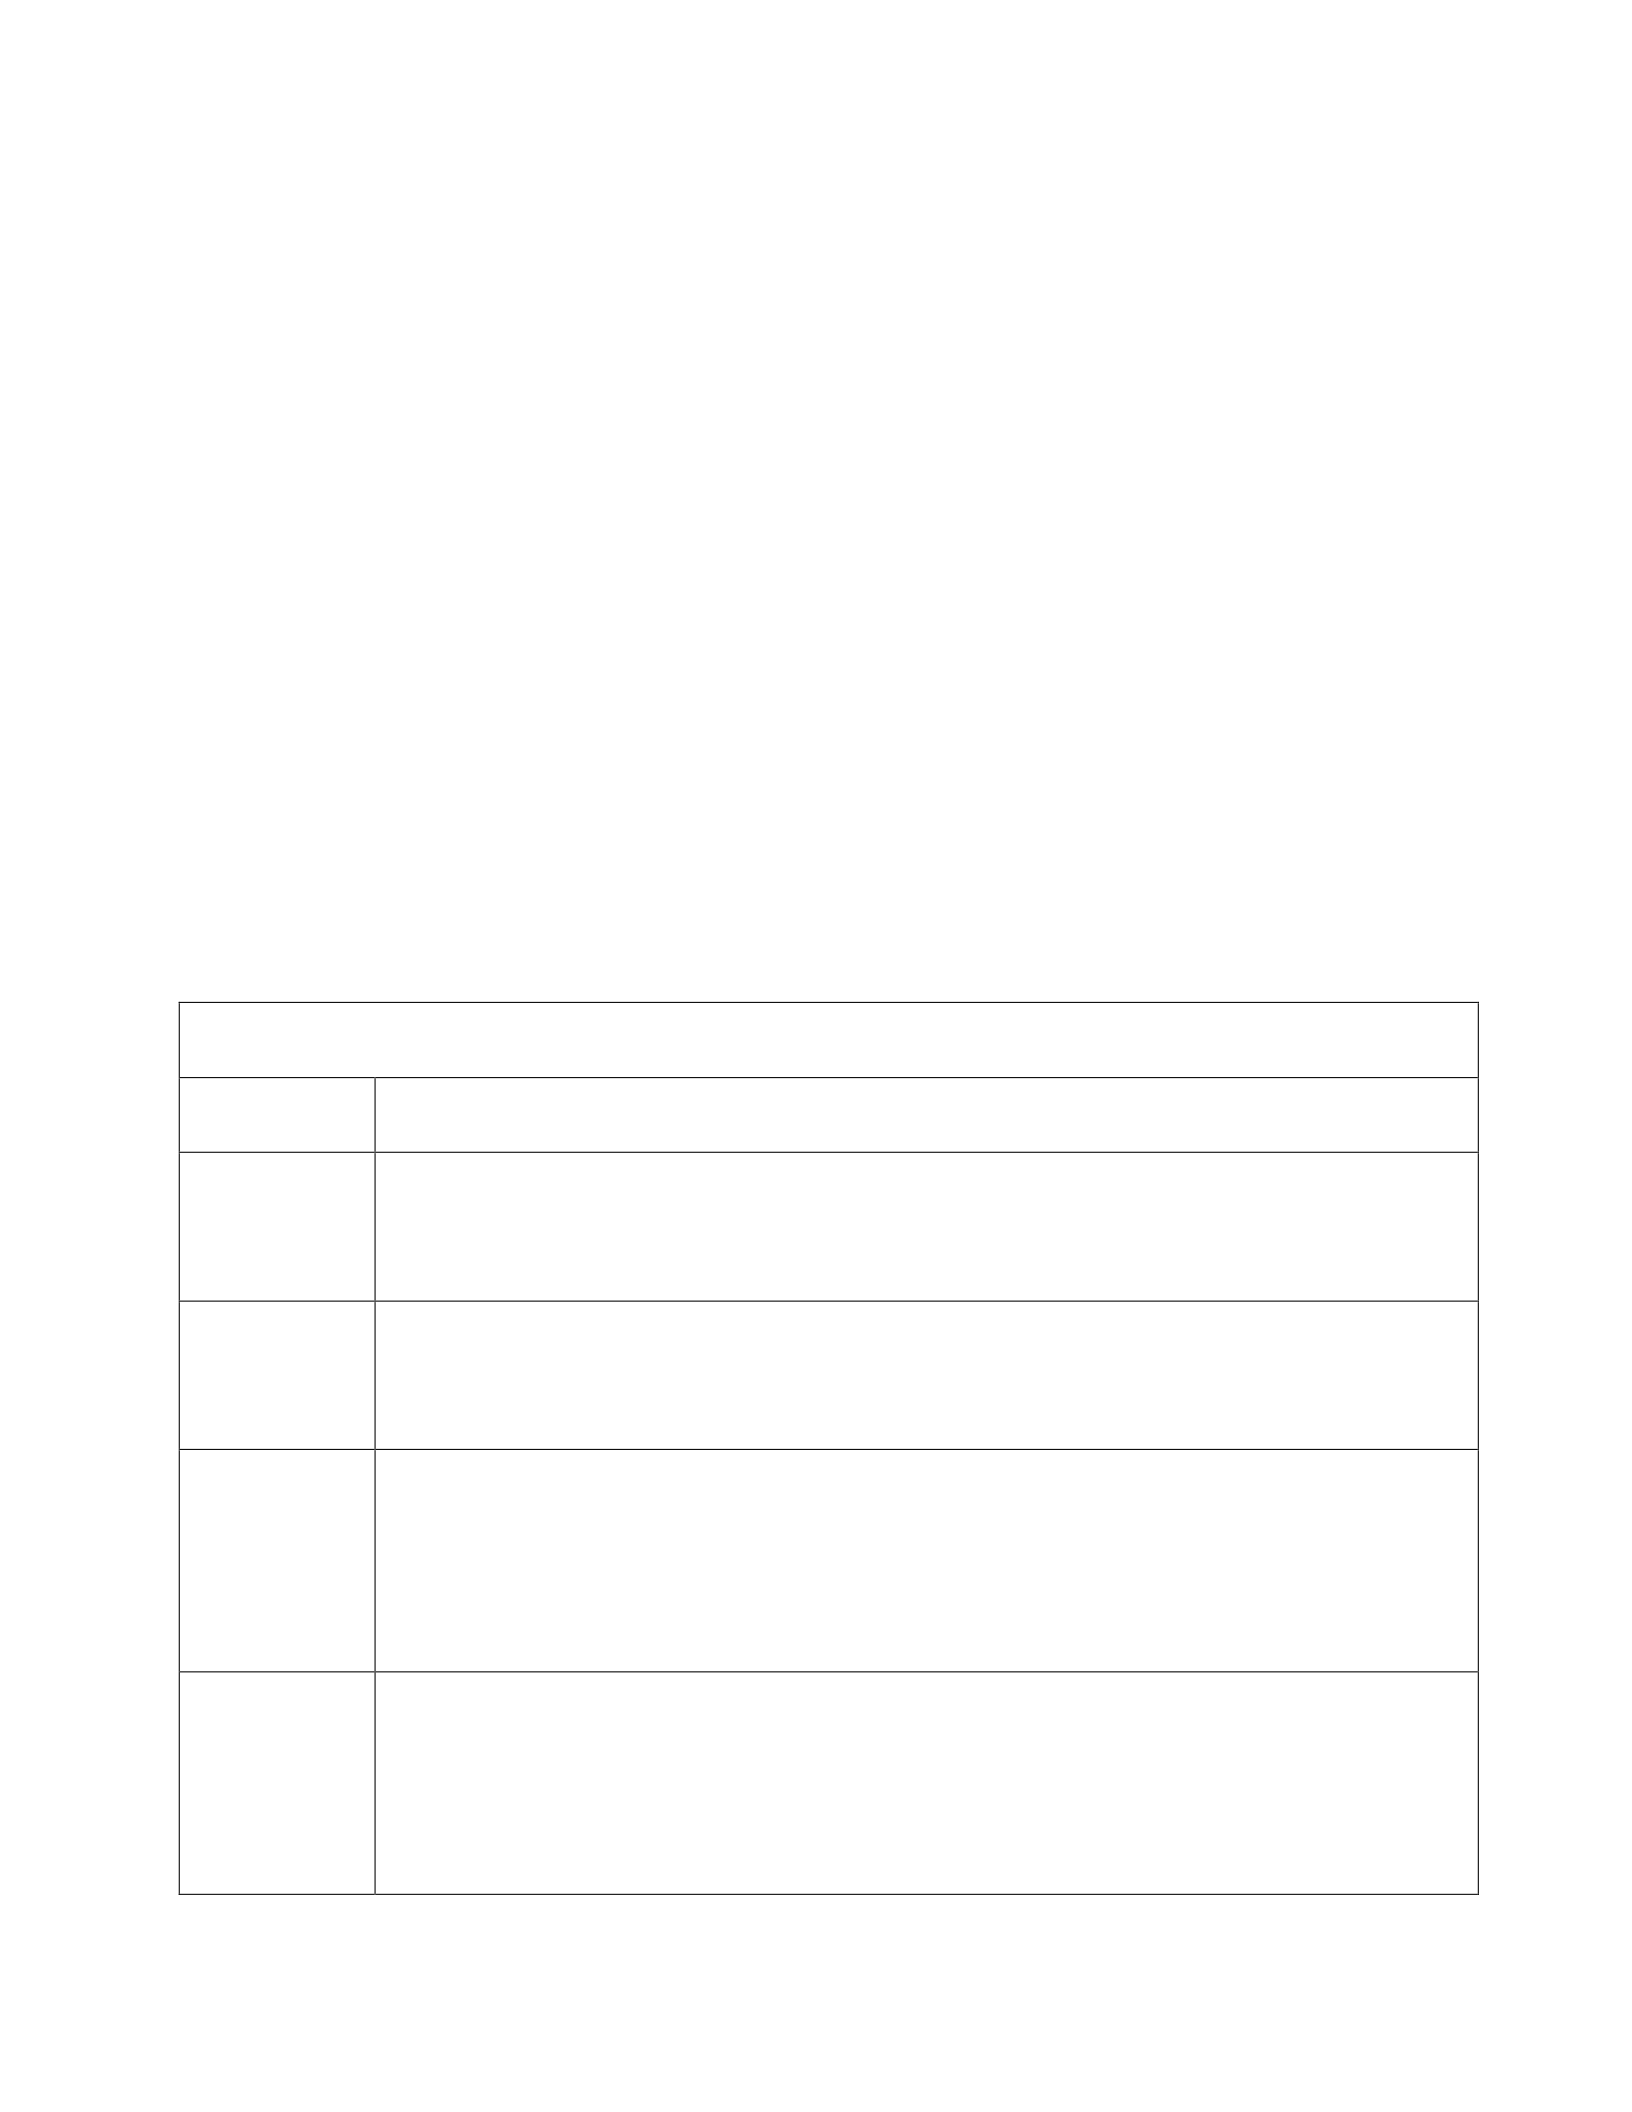
Table 3: Causes of scapula dyskinesis
Because
Related pathologies
Bone
kyphosis toraks, fraktur klavikula nonunion, klavikula mal-union dipersingkat,
Fracture shape
Neurological
cervical radiculopathy; long thorax, dorsal scapular nerve, or spinal accessory
nerve paralysis
Joint
high-level air conditioning instability, air conditioning arthrosis, internal disorders of
the GH joint (labral
injury), glenohumeral instability, biceps tendinitis
Soft tissue
inflexibility (tightness) or intrinsic muscle problems. Inflexibility and stiffness of
the pectoralis minor and short bicep head can lead to anterior tilt and protraction
due to its attraction to the coracoid

20
Soft tissue posterior shoulder inflexibility can lead to glenohumeral internal rotation
deficit (GIRD), shoulder rotation tightness (GIRD and Total Range of Motion Deficit)
and pectoralis-small inflexibility
Muscle
Periscapular muscle activation serratus anterior activation and decreased strength
Upper trapezius / lower trapezius force pairs can be changed Delayed onset of
activation in the lower trapezius
inferior trapezius weakness and anterior serratus, upper trapezius hyperactivity or
scapular muscle detachment and kinetic chain factors including hip/leg weakness and
core weakness

21
The cause of scapula discinesis remains multifactorial (Table 3), but altered scapula movement
or position reduces the linear size of the subacromial space (Giphart, van der Meijden, & Millett,
2012), increases impact symptoms (Kibler, Ludewig, McClure, Michener, Bak, & Sciascia, 2013),
decreases the rotator cuff strength (Kebaetse, McClure, & Pratt, 1999; Smith, Dietrich, Kotajarvi,
& Kaufman, 2006; Kibler, Sciascia, & Dome, 2006) and increases the risk of internal collisions
(Kibler & Sciascia, 2010).
However, there are no conclusive studies showing the occurrence of scapular dyskinesis
occurring as a direct result of lower trapezius muscle fatigue, although the scapular orientation
changes in the direction of the collision (downward rotation, anterior tilt, and protraction), has
been reported with fatigue (Birkelo, Padua, Guskiewicz, & Karas, 2003; Su, Johnson, Gravely, &
Karduna, 2004; Madsen, Bak, Jensen, & Welter, 2011; McQuade, Dawson, & Smidt, 1998;
Suzuki, Swanik, Bliven, Kelly, & Swanik, 2006; Tyler, Cuoco, Schachter, Thomas, & McHugh,
2009; Chopp, Fischer, & Dickerson, 2011; Tsai, McClure, & Karduna, 2003; Joshi, Thigpen,
Bunn, Karas, & Padua, 2011; Noguchi, Chopp, Borgs, & Dickerson, 2013; Madsen, Bak, Jensen,
& Welter, 2011; Chopp, Fischer, & Dickerson, 2011). Determining the effects of upper extremity
muscle fatigue and the mechanisms associated with subachromial space reduction is important
from the perspective of prevention and rehabilitation. However, changes in scapular orientation
after targeted fatigue of the scapular-stabilizing lower trapezius muscles have not been verified at
this time, but one study (Borstad, Szucs, & Navalgund, 2009) used ''modified push-ups plus'' as
the fatigue protocol, which elicited fatigue from the anterior serratus, upper and lower trapezius
muscles, and infraspinatus. Kinematics resulting from fatigue include a decrease in posterior tilt
(-3.8°), increased internal rotation (protraction) (+3.2°), and no upward rotation change. Prone rowing
exercise, in which the patient lies on his stomach on a bench and flexes his elbows from 0° to

22
90° while the shoulder flexion angle moves from 90° to 0° using resistive loads, it is clinically
recommended to strengthen the scapular stabilizer while activating the rotator cuff minimally
(Escamilla, et al., 2009; Reinold, et al., 2004). Research (Noguchi, Chopp, Borgs, & Dickerson,
2013) investigated the ability of this susceptible rowing task to target only scapula stabilizers to
help clarify whether scapula discinement is a possible mechanism of fatigue-induced
subachromial impingement risk. However the authors (Noguchi, Chopp, Borgs, & Dickerson,
2013) show no significant change in the orientation of the 3-Dimensional scapula. This result may
be due to the fact that tummy rowing exercises have a moderate to minimal EMG activation
profile of the lower trapezius (45±17% MVIC; Ekstrom, Donatelli, & Soderberg, 2003) and
(67±50%MVIC; Moseley, Jobe, Pink, Perry, & Tibone, 1992). Tummy rowing has a maximum
activation of the upper trapezius (112±84%MVIC; Moseley, Jobe, Pink, Perry, & Tibone, 1992
and 63±17%MVIC; Ekstrom, Donatelli, & Soderberg, 2003), middle trapezius (59±51%MVIC;
Moseley, Jobe, Pink, Perry, & Tibone, 1992 and 79±23%MVIC; Ekstrom, Donatelli, &
Soderberg, 2003), and levator skapulae (117±69%MVIC; Moseley, Jobe, Pink, Perry, & Tibone,
1992). Therefore, it is difficult to show significant changes in the movement of the scapular when
the primary scapular stabilizer (lower trapezius) is not specifically targeted in the grueling
exercise.
Therefore, paddling on the stomach or similar exercises intended to activate the stabilizing
muscles of the scapula, while at least activating the rotator cuff, failed to do so, suggesting that
the correct muscles that contribute to maintaining healthy glenohumeral and scapulothoracic
kinematics are not targeted.

23
2.3 LIMITATIONS OF STUDYING EMG IN THE SHOULDER MUSCLES
Abnormal muscle activity patterns have been observed in overhead athletes with impact
(Lukaseiwicz, McClure, Michener, Pratt, & Sennett, 1999; Ekstrom, Donatelli, & Soderberg,
2003; Ludewig, & Cook, 2000) and electromyography analysis (EMG) were used to assess muscle
activity in the shoulder (Kelly, Backus, Warren, & Williams, 2002). Fine-wire EMG (fw) and
surface EMG have been used to indicate changes in muscle activity (Jaggi, et al., 2009) and the
study of muscle function through EMG helps measure muscle activity by recording muscle
electrical activity (Solomonow, et al., 1994). In general, the electrical activity of the motor units
of individual muscles is measured and therefore the more active the motor unit, the greater its
electrical activity. The choice of electrode type is usually determined by the size and location of
the muscle investigated with fwEMG used for deep muscles and sEMG used for superficial
muscles (Jaggi, et al., 2009). It is also important to note that it may be difficult to test in the exact
same area for fwEMG and sEMG, as both stick to the skin and the skin can move over the muscles.
Jaggi (Jaggi, et al., 2009) examined the degree of agreement on sEMG and fwEMG in
infraspinatus, pectoralis major, latissimus dorsi, and anterior deltoid of 18 subjects with a
diagnosis of shoulder instability. Although this study had no controls, sEMG and fwEMG showed
poor agreement rates but sensitivity and specificity for infraspinatus were good (Jaggi, et al.,
2009). However, this article points to poor strength, lack of control group, and possible
investigator bias. In this article, two different researchers performed five identical uniplanar
movements, but at different times the biases of individual researchers may have influenced the
level of agreement in this study. Also, a diagnosis of shoulder instability is a multifactorial
diagnosis that may or may not include pain and that may also contain secondary pathologies such
as RTC tears, labral tears, shoulder impingements, and various types of instability (including

24
anterior, inferior, posterior, and superior instability).
In a study by Meskers and colleagues (Meskers, de Groot, Arwert, Rozendaal, & Rozing,
2004), 12 subjects without shoulder pathology underwent sEMG and fwEMG testing of 12
shoulder muscles while performing various upper extremity movements. Also, some subjects
were retested again on days 7 and 14 and this method showed sufficient accuracy for intra-
individual measurements on different days. Therefore, this article provides some support for the
use of EMG tests on shoulder muscles before and after the intervention.
In general, sEMG may be more representative of the overall activity of a particular muscle,
but the disadvantage is that some of the measured electrical activity may come from other
unstudied muscles, a phenomenon called crosstalk (Solomonow, et al., 1994).
Generally, sEMG can take up 5-15% of electrical activity from unstudied surrounding muscles
and subcutaneous fat can also affect crosstalk in sEMG amplitudes (Solomonow, et al., 1994;
Jaggi, et al., 2009). Inconsistencies in the interpretation of sEMG arise from differences in the
subcutaneous fat layer, familiarity with the test exercise, the actual level of individual tension
during movement, or other physiological factors.
The methodological inconsistencies of EMG testing include the accuracy of skin
preparation, distance between electrodes, electrode localization, electrode type and orientation,
and normalization method. The standard for normalizing EMG is the calculation of relative
amplitude, referred to as the maximum voluntary contraction rate (MVC) (Anders, Bretschneider,
Bernsdorf, & Schneider, 2005). However, some studies have shown non-linear amplitude due to
recruitment strategies and contraction rates (Anders, Bretschneider, Bernsdorf, & Schneider,
2005).
Maximum voluntary isometric contractions (MVIC) have also been used in the
normalization of EMG data. Knutson et al. (Knutson, Soderberg, Ballantyne, & Clarke, 2005)

25
found that The MVIC normalization method shows lower variability and higher inter-individual
reliability compared to dynamic contraction MVC. The overall conclusion is that MVIC is the
standard for normalization in normal populations and orthopedic disorders. When comparing
EMG between subjects, EMG is normalized to MVIC (Ekstrom, Soderberg, & Donatelli, 2005).
When testing EMG in orthopedically impaired healthy overhead athletes, muscle length,
bone position, and muscle contraction can all add variance to the observed final action. Intra-
individual errors between movements and between groups (healthy vs. pathological) and intra-
observer variance can also add variance to the results. Pain in pathological populations may not
allow individuals to perform certain movements, which is a particular limitation for this
population. In addition, MVIC testing is a static test, which can be used for dynamic testing but
allows comparisons between subjects. Kelly and his colleagues (Kelly, Backus, Warren, &
Williams, 2002) have described 3 progressive levels of EMG activity in shoulder patients. The
authors suggest that the minimum reading is between 0-39% MVIC, the moderate reading is
between 40-74% MVIC, and the maximum reading is between 75-100% MVIC.
When dealing with recording EMG while performing therapeutic exercises, changing the
length of the muscles and the speed of contraction is a problem that must be addressed because it
can affect the magnitude of the EMG signal (Ekstrom, Donatelli, & Soderberg, 2003). This can
be overcome by controlling the speed of movement performed because it has been shown that
there is a close linear relationship between force production and EMG recording in concentric and
eccentric contractions at constant speeds (Ekstrom, Donatelli, & Soderberg, 2003). The use of
metronomes has been used in previous studies to overcome the speed of movement and maintain
a constant rate of speed.

26
2.4 DYNAMICS OF THE SHOULDER AND SCAPULA
Shoulder dynamics result from the interaction of complex muscle, bone, and support
structures, which provide a range of motion that exceeds that of other joints in the body and
maintain proper control and stability of all joints involved. The resting position of the
glenohumeral joint and its supporting structure static alignment is influenced by the alignment of
the static thoracic spine, the humer bone component, the scapular bone component, the clavicle
bone component, and the muscular attachment of the thoracic and cervical spine (Wilk, Reinold,
& Andrews, 2009).
Changes in shoulder range of motion (ROM) have been associated with shoulder
impingement along with scapula discinesis, (Lukaseiwicz, McClure, Michener, Pratt, Sennett,
1999; Ludewig & Cook, 2000; Endo, Ikata, Katoh, & Takeda, 2001) clavicle movement, and
improved translation of the humerus head (Ludewig & Cook, 2002; Laudner, Myers, Pasquale,
Bradley, & Lephart, 2006; McClure, Michener, & Karduna, 2006; Warner, Micheli, Arslanian,
Kennedy, & Kennedy, 1992; Deutsch, Altchek, Schwartz, Otis, & Warren, 1996; Lin, et al., 2005).
All of these irregularities are believed to reduce the subacromial space or approach the subsurface
tendon to the glenoid labrum, creating a decrease in the clearance of the RTC tendon and other
structures beneath the acromion (Graichen, et al., 1999). This altered shoulder kinematics leads to
a change in the activation pattern of the shoulder and scapular muscles or a change in the length
of rest of the shoulder muscles.
2.4.1 Shoulder/scapular movements
Normal shoulder biomechanics have been studied with EMG during ROM (Ludewig &
Cook, 2000; Kibler & McMullen, 2003; Bagg & Forrest, 1986), cadaver studies (Johnson,
Bogduk, Nowitzke, & House, 1994), patients with nerve injury (Brunnstrom, 1941; Wiater &
27
Bigliani, 1999), and in predictive biomechanical modeling of the arm and muscle function
(Johnson, Bogduk, Nowitzke, & House, 1994; Poppen & Walker, 1978). This approach has
perfected our knowledge of the function and movement of the shoulder and scapula muscles.
Understanding muscle adaptation to pathology in the shoulder is important for developing
intervention guidelines to improve shoulder function. The study has defined a general consensus
on what muscles will be active and when during the normal range of motion of the shoulder.
In 1944 Inman (Inman, Saunders, & Abbott, 1944) discussed the "scapulohumeral rhythm",
which is the ratio of the glenohumeral joint "2:1" to the range of motion of the scapulothoracic
joint during the active range of motion. Therefore, if the glenohumeral joint moves 180 degrees of
abduction then the scapula rotates 90 degrees. However, this ratio does not take into account
different planes of motion, velocity of motion, or loaded motion and therefore this 2:1 ratio has
been debated in the literature with many authors recently reporting a range of scapulohumeral ratios
(Table 4) from 2.2:1 to 1.7:1 with some reporting larger ratios of 3:2 (Freedman & Munro, 1966)
and 5:4 (Poppen & Walker, 1976). Many of these differences may be due to different measurement
techniques and different methodologies in the study. McQuade Leads
Table 4: Scapulohumeral ratio during shoulder elevation
Tahun Studi
Scapulohumeral ratio
Fung et al. 2001
2.1/1
Ludewig dkk. 2009
2.2/1
McClure dkk. 2001
1.7/1
Inman dkk. 1944
2:1
Freedman & Monro 1966
3:2
Poppen & Walker 1976
1.24:1 or 5:4
Moron
28
McQuade & Smidt 1998
7.9:1 to 2.1:1 (PROM) 1.9:1 to 4.5:1
(loaded)

29
colleagues (McQuade & Smidt, 1998) also reported that the 2:1 ratio does not adequately explain
normal shoulder kinematics. However, McQuade and colleagues did not look at submaximally
loaded conditions, pathological populations, EMG activity during testing, but only looked at
concentric phases that would all limit the clinical application of the study results.
There is also disagreement about when this 2:1 scapulohumeral ratio occurs although it is
generally considered to occur at 60 to 120 degrees with 1 degree of scapular movement occurring
for every 2 degrees of elevation movement up to 120 degrees and after that 1 degree of scapular
movement for every 1 degree of elevation movement (Reinold, Escamilla, & Wilk, 2009). Contrary
to common consideration, some authors have recorded the greatest scapular movement at 30 to 60
degrees while others have found the greatest movement at 80 to 140 degrees, but generally these
differences are due to different measurement techniques (Bagg & Forrest, 1986).
Normal scapular movement during glenohumeral elevation helps maintain the correct long
tension relationship of the shoulder muscles and prevents subachromial structures from being
impacted and generally includes upward rotation, external rotation, and posterior tilt on the chest
with upward rotation being the dominant movement (McClure, et al., 2001; Ludewig & Reynolds,
2009). Overhead athletes generally exhibit increased upward rotation of the scapular, internal
rotation, and retraction during elevation and this is hypothesized as an adaptation to allow for the
cleaning of subachromial structures during the throw (Wilk, Reinold, & Andrews, 2009).
Generally accepted normal ranges have been observed for upward rotation of the scapular (45-55
degrees), posterior tilt (20-40 degrees), and external rotation (15-35 degrees) during elevation and
the scapular muscles are essential in maintaining the scapulohumeral

30
kinematic equilibrium because they cause scapular motion (Wilk, Reinold, & Andrews, 2009;
Ludewig & Reynolds, 2009).
However, the amount of internal scapular rotation during elevation has shown a lot of
variability across investigations, elevation planes, subjects, and points in the range of motion of
the glenohumeral. The authors suggest that a slight increase in the internal rotation of the scaluka
may be normal at the beginning of the glenohumeral elevation (McClure, Michener, Sennett, &
Karduna, 2001) and is also generally accepted (but has limited evidence to support) that the
elevation of the final range involves the external rotation of the scapula (Ludewig & Reynolds,
2009).
Scapulothoracic "translation" (Figure 2) also occurs during arm elevation and includes
elevation/depression and adduction/abduction (retraction/protraction), which originates from
clavicle movement. Also scapulothoracic kinematics involves a combination of acromioclavicular
(AC) and sternoclavicular (SC) joint movements, therefore, the authors have conducted a study on
3D motion analysis of AC and SC joints in healthy subjects and have linked scapulothoracic
elevation with SC elevation and scapulothoracic abduction/adduction with SC
protraction/retraction (Ludewig & Reynolds, 2009).
Figure 2: Scapulothoracic translation during arm elevation

31
Despite many of these scapular movements, there are still gaps in the literature and
unanswered questions including: 1) which muscles are responsible for the internal/external
rotation or anterior/posterior tilt of the scapula, 2) what is the normal value for
protraction/retraction 3) what is the normal value for scapulothoracic elevation/depression, 4) how
do we measure scapulothoracic "translation"?
2.4.2 Loaded vs unloaded
The effects of external load on the hand during elevation are still unclear on the mechanics
of the scapula, scapulohumeral ratio, and EMG activity of the scapula muscles. Adding 5kg of
weight in the hands while performing shoulder movements has been shown to improve the EMG
activity of the shoulder muscles. In a study of 16 subjects by Antony and Keir (Antony & Keir,
2010), subjects performing scaptions with a weight of 0.5kg added to the hands and shoulders
increased by 4% in all postures and speeds. Also, when the subject used a stronger grip on the
load, a 2% decrease was shown in the anterior and middle deltoids, and a 2% increase was seen
in the posterior and trapezius deltoid infraspinatus, and finally the biceps increased by 6% MVE.
While this study provides some evidence for the use of exercises that are burdened with a firmer
grip on the dumbbells when performing rehabilitation, the study had limited participants and was
only conducted in a young and healthy population which limited the clinical application of the
results.
Some researchers have shown no change in the scapulothoracic ratio with the addition of
resistance (Freedman & Munro, 1966), while others have reported a different ratio with the
addition of resistance (McQuade & Smidt, 1998). However, some limitations noted in the
McQuade & Smidt study include: 1) submaximal loads were not investigated; 2) pathological
population is not assessed; 3) EMG analysis is not performed; and 4) only concentric movements

32
that
Investigated. All these shortcomings limit the results of the study in pathological populations
and more research is needed on the effect of burden on scapulohumeral ratios.
Witt and colleagues (Witt, Talbott, & Kotowski, 2011) examined the activity of upper,
middle, and lower trapezius EMGs, and anterior serratus with a 3-pound dumbbell weight and
elastic resistance during a diagonal movement pattern in 21 healthy participants. They concluded
that the type of resistance did not significantly alter the muscle activity in the diagonal pattern
tested. However, the study showed limitations that would change the interpretation including: 1)
the exercise/fitness level of the study population was not determined; 2) the resistance selection
procedure does not use the maximum percentage of repetition of any kind; and 3) there may be a
crosstalk with sEMG selection.
2.4.3 Scaular vs. other planes
The scapular plane is located 30 to 40 degrees anterior to the coronal plane, which offers
both biomechanical and anatomical features. At the elevation of the scapula plane, the joint
surfaces have a greater fit, the inferior shoulder capsule ligament and the RTC tendon remain
untwisted, and the supraspinatus and deltoid are favorably aligned for elevation rather than flexion
and/or abduction (Dvir & Berme, 1978). In addition to these advantages, the scapula field is where
most of the functional activities are carried out and is also the optimal field for shoulder
strengthening exercises. When performing strengthening exercises in the scapula plane, shoulder
rehabilitation is improved because the unwanted passive strain on the RTC tendon and the
glenohumeral joint capsule is at its lowest point and much lower than flexion and/or abduction
(Wilk, Reinold, & Andrews, 2009). The upward rotation of the scapular is also greater in the
scapular plane, which will decrease during elevation, but will allow for more "cleaning in the

33
subachromial space" and reduce the risk of impact.
2.4.4 Scapulothoracic EMG Activity
Previous studies have also examined the activity of scapulothoracic EMG and kinematics
simultaneously to link the functional status of muscles to scapula mechanics. In general during
normal shoulder elevation, the scapula will rotate upwards and tilt backward on the thorax. The
internal rotation of the scapula has also been studied but shows variability throughout the
investigation (Ludwig & Reynolds, 2009).
A general consensus has been established regarding the role of the scapula muscle during
arm movements even with various approaches (different electrode positions on the muscles during
EMG analysis [Ludwig & Cook, 2000; Lin, et al. 2005; Ekstrom, Bifulco, Lopau, Andersen, &
Gough, 2004), different normalization techniques (McLean, Chislett, Keith, Murphy, & Walton,
2003; Ekstrom, Soderberg, & Donatelli, 2005), varying rates of contractions, different types of
contractions, and varying muscle lengths during contractions. Although EMG activity does not
determine whether a muscle stabilizes, translates, or rotates a joint, it does indicate how active the
muscle is during movement. Even with these various approaches and confounding factors, it is
generally understood that trapezius and anterior serratus (middle and inferior) can stabilize and
rotate the scapula (Bagg & Forrest, 1986; Johnson, Bogduk, Nowitzke, & House, 1994;
Brunnstrom, 1941; Ekstrom, Bifulco, Lopau, Andersen, Gough, 2004; Inman, Saunders, &
Abbott, 1944). Also during arm elevation, the scapulothoracic muscles produce an upward rotation
and resist the downward rotation acting on the scapula (Dvir & Berme, 1978). Three muscles
including trapezius (upper, middle, and lower), pectoralis, minor, and anterior serratus (middle,
lower, and upper) have been observed using EMG analysis.

34
In previous studies, trapezius has been responsible for stabilizing the scapula because the
middle and lower fibers are perfectly aligned to produce an external rotation of the scapula that
facilitates the stabilization of the scapula (Johnson, Bogduk, Nowitzke, & House, 1994). Also,
trapezius is more active during kidnapping versus flexion (Inman, Saunders, & Abbott, 1944;
Wiedenbauer & Mortensen, 1952) due to a decrease in the internal rotation of the scapula in the
abduction of the scapula plane. The upper trapezius is most active with scapular elevation and is
produced through clavicular elevation. The lower trapezius is the only part of the trapezius that can
rotate the scapula upwards while the middle and lower trapezius are well suited for scapular
stabilization and external rotation of the scapula.
Another important muscle is the anterior serratus which can be broken down into upper,
middle, and lower groups. The anterior fibers of the middle and lower serratus are oriented in
such a way that they are at a substantial mechanical advantage for upward rotation of the scapular
(Dvir & Berme, 1978) in combination with the ability to tilt posteriorly and rotate the scapula
externally. Therefore, the middle and lower anterior serratus are the main drivers for scapular
rotation during arm elevation and they are the only muscles that can tilt the scapula in the chest
posteriorly. Finally, the upper serratus has been investigated to a minimum (Ekstrom, Bifulco,
Lopau, Andersen, Gough, 2004).
Pectoralis minor can produce downward scapular rotation, internal rotation, and anterior
tilt (Borstad & Ludewig, 2005) as opposed to upward rotation and posterior tilt during arm
elevation (McClure, Michener, Sennett, & Karduna, 2001). Previous studies (Borstad & Ludewig,
2005) have shown that a decrease in the length of the minor pectoralis reduces posterior tilt and
increases internal rotation during arm elevation which increases the risk of impact.

35
2.4.5 Glenohumeral EMG Activity
In addition to the scapulothoracic muscles, the glenohumeral muscles including the deltoid
and rotator cuff (supraspinatus, infraspinatus, subscapularis, and teres minor) are contributors to
the proper function of the shoulder. Deltoids are the main movers in elevation and were initially
aided by the supraspinatus (Sharkey, Marder, & Hanson, 1994). The rotator cuff stabilizes the
glenohumeral joint against excessive translations of the humerus head through medially directed
compression of the humerus head into the glenoid (Sharkey & Marder, 1995). The subscapularis,
infraspinatus, and teres minor have inferiorly directed lines of action that compensate for the
superior translational component of the deltoid muscle (Sharkey, Marder, & Hanson, 1994).
Therefore, the right balance between the increasing and decreasing forces results in (1-2mm)
superior translation of the humerus head during elevation. Finally, the infraspinatus and minor
terraces generate an external rotation of the humerus' head during the elevation of the arms.
2.4.6 Shoulder EMG activity with impact
In addition to experiencing pain and other deficits, a decrease in EMG activation of many muscles
has been observed in patients with shoulder impingement. In patients with shoulder impingement,
the decrease in overall anterior serratus activity from 70 to 100 degrees and the decrease in the
activation of the lower anterior serratus from 31 to 120 degrees on the elevation of the scapular
plane arm (Ludwig & Cook, 2000). Upper trapezius has also shown a decrease in activity between
40 to 100 degrees and an increase in upper and lower trapezius activity from 61 to 120 degrees
when performing scaptions (Ludwig & Cook, 2000; Peat & Grahame, 1977).
Increased activation of the upper trap is consistent (Ludwig & Cook, 2000; Peat & Grahame, 1977)
and is associated with an increase in claccular elevation or scapular elevation found in the study
(McClure, Michener, & Karduna, 2006; Kibler & McMullen, 2003). It increases the elevation of

36
the clavicle in SC joints can be produced by increased upper trapezius activity (Johnson, Bogduk,
Nowitzke, & House, 1994) and produce a scapular anterior tilt that causes a potential mechanism
to cause or worsen impingement symptoms. In conclusion, the weakness of the middle and lower
serratus or decreased activity contributes to the impingement syndrome. This improvement in
muscle function can reduce pain and dysfunction in shoulder impingement patients.
Changes in the activation of the rotator cuff muscles have been seen in patients with
impingement. Decreased deltoid and rotator cuff activity is not felt in the initial area of movement
(Reddy, Mohr, Pink, & Jobe, 2000). However, the infraspinatus, supraspinatus, and middle
deltoid showed a decrease in activity from 30-60 degrees, a decrease in infraspinatus activity from
60-90 degrees, and no significant difference was seen from 90-120 degrees. This decrease in
activity is theorized to be related to inadequate head humerus depression (Reddy, Mohr, Pink, &
Jobe, 2000). Other studies show that impact decreases the activity of the subscapularus,
supraspinatus, and infraspinatus; increased activation of the middle deltoid from 0-30 degrees;
decrease in coactivation of the supraspinatus and infraspinatus from 30-60 degrees; and increased
infraspinatus, subscapularis, and supraspinatus activation from 90-120 degrees (Myers, Hwang,
Pasquale, Blackburn & Lephart, 2008). Overall, impact led to decreased RTC coactivation and
increased deltoid activity at elevation initiation (Reddy, Mohr, Pink, & Jobe, 2000; Myers,
Hwang, Pasquale, Blackburn, & Lephart, 2008).
2.4.7 Normal shoulder EMG activity
Normal Shoulder EMG activity will allow for proper shoulder function and maintain
adequate clearance of subacromial structures during shoulder function and elevation (Table 5).
The scapulohumeral muscles are essential for providing movement, providing dynamic
stabilization, and providing proper coordination and sequencing in the glenohumeral complex
37
Overhead athletes due to the complexity and movement required in overhead sports. Since the
glenohumeral and scapulothoracic joints are attached by muscles, the muscle activity of the
muscles of the shoulder complex can be correlated with the maintenance of the scapulothoracic
rhythm and the maintenance of the shoulder force pair including: 1) Deltoid-rotator cuffs; 2)
Upper trapezius and anterior serratus; and 3) anterior posterior rotator cuffs.
Table 5: Mean glenohumeral EMG normalized by MVIC during scaptions with neutral rotation
(Adapted from Alpert, Pink, Jobe, McMahon, & Mathiyakom, 2000).
Interval
Former
Deltoid
EMG
Tengah
Deltoid
EMG
Posterior
Deltoid
EMG
Supraspin
atus EMG
(%MVIC)
Infraspina
tus EMG
(%MVIC)
EMG
Teres
Minor
(%MVIC)
Subscapul
aris EMG
(%MVIC)
(%MVIC
(%MVIC)
(%MVIC)
)
0-30°
22±10
30±18
2±2
36±21
16±7
9±9
6±7
30-60 °
53±22
60±27
2±3
49±25
34±14
11±10
14±13
60-90 °
68±24
69±29
2±3
47±19
37±15
15±14
18±15
90-120 °
78±27
74±33
2±3
42±14
39±20
19±17
21±19
120-150 °
90±31
77±35
4±4
40±20
39±29
25±25
23±19
During the initial arm elevation, the stronger deltoids exert force upwards and outwards
on the humerus. If this force would occur without opposition then superior migration of the
humerus would occur and result in a 60% stretch and increase in pressure of the structure between
the greater tuberosity and the acromion when the rotator cuff did not work properly (Ludewig &
Cook, 2002). While the direction of the RTC force vector is debated parallel to the axillary
boundary (Inman, et al., 1944) or perpendicular to the glenoid (Poppen & Walker, 1978), the

38
overall effect is that of a force vector that counteracts the deltoid.
On normal healthy shoulders, Matsuki and colleagues (Matsuki, et al., 2012) showed
2.1mm mean superior migration of the humerus head from 0-105° elevation and mean inferior
translation 0.9mm from 105-180° in elevation during shoulder fluoroscopic images of 12 male
subjects. The deltoid-rotator cuff style pair exists when the superior directional force of the deltoid
is countered by the inferior force and directed medially from the infraspinatus, subscapularis, and
minor terraces. Supraspinatus also exerts a compressive force on the humerus to the glenoid,
therefore serving a close role in force pairs (Inman, Saunders, & Abbott, 1944). These RTCs help
neutralize the upward shear force, reduce the workload on the deltoid through increased
mechanical superiority (Sharkey, Marder, & Hanson, 1994), and aid in stabilization. Previous
authors have also shown that fatigue or tearing of the RTC will increase superior migration of the
humerus head (Yamaguchi, et al., 2000) which indicates the importance of properly functioning
force pairs.
The second force pair, the synergistic relationship between the upper trapezius and the
anterior serratus, exists to produce an upward rotation of the scapula during shoulder elevation
and a server of 4 functions: 1) allows the rotation of the scapula, maintaining the glenoid surface
for optimal position; 2) maintain an efficient long-voltage relationship for deltoid; 3) prevent the
impact of the rotator cuff from the subacromial structure; and 4) provide a stable scapular base
that allows for proper recruitment of scapulothoracic muscles. The center of momentary rotation
begins near the medial border of the scapular spine at lower elevation levels and therefore the
lower trapezius has a small lever arm because its distal attachment is near the center of rotation.
However, during sustained elevation, the center of momentary rotation moves laterally along the
spine towards the acromioclavicular joint and therefore at higher abduction rates (≥90°) the lower

39
trapezius will have a larger and larger lever arm influence on upward rotation and scapular
stabilization, along with anterior serratus (Bagg & Forrest, 1988).
Overall, the position of the scapula is important for centering the head of the humerus on
the glenoid which creates a stable foundation for shoulder movement in athletes above the head
(Ludwig & Reynolds, 2009). In a healthy shoulder, the force pair between the anterior serratus and
the trapezius rotates the scapula which maintains the glenoid surface in an optimal position,
positions the deltoid muscle in an optimal long-tension relationship, and provides a stable
foundation (Wilk, Reinold, & Andrews, 2009). A properly functioning force pair will prevent the
impact of subacromial structures on the coracoacromial arch and allow the deltoid and
scapulothoracic muscles to generate more strength, stability, and strength (Wilk, Reinold, &
Andrews, 2009). Muscle imbalances from weakness or shortening can result in changes in these
pairs of strength, which contribute to impaired shoulder stabilization and may lead to impingement.
The anterior-posterior RTC force pair creates inferior dynamic stability (compressing the
humerus head) and a basin compression mechanism (compressing the humerus head in the glenoid)
due to the relationship between anterior-based subscapularis and minor terraces and posterior-
based infraspinatus. Imbalances have been shown in overhead athletes due to overdeveloped
internal rotators and underdeveloped external rotators in the shoulders.
2.4.8 Abnormal scapulothoracic EMG activity
Although no significant changes were noted in the resting scapular position of the impact
population (Ludewig & Cook, 2000; Lukaseiwicz, McClure, Michener, Pratt, & Sennett, 1999)
changes in upward scapular rotation, posterior tilt, clavicle elevation/retraction, internal scapular
rotation, scapula symmetry, and scapulohumeral rhythm have been observed (Ludewig &
Reynolds, 2009; Lukasiewicz, McClure, Michener, Pratt, & Sennett, 1999; Ludewig & Cook,

40
2000; McClure, Michener, & Karduna, 2006; Endo, Ikata, Katoh, & Takeda, 2001). Overhead
athletes have also shown a link between scapulothoracic muscle imbalance and altered scapular
muscle activity has been associated with SIS (Reinold, Escamilla, & Wilk, 2009).
SAS has been associated with changes in scapula kinematics when lifting the arm called
scapula discinesis, which is defined as an observable change in the position of the scapula and the
pattern of scapula movement in relation to the thoracic cage. J.P. Warner coined the term scapula
discinesis and Ben Kibler described a classification system that outlines 3 primary scapula
dysfunctions that name conditions based on the most prominent or most visible part of the scapula
when viewed during clinical examination.
Burkhart and his colleagues (Burkhart, Morgan, & Kibler, 2003) also coined the term
SICK (Scapular malposition, Inferior medial border prominence, Coracoid pain and malposition,
and dyskinesis of scapular movement) scapula to describe the asymmetrical malposition of the
scapula in throwing athletes.
At normal healthy arm elevation, the scapula will rotate upwards, tilt posteriorly, and
rotate externally and many authors have studied changes in scapular motion with SAS (Table 6).
The current literature is conflicting with respect to specific deviations from the movement of the
scapula in the SAS population. Researchers have reported a decrease in posterior slope in SAS
populations (Lukasiewicz, McClure, Michener, Pratt, & Sennett, 1999; Ludewig & Cook, 2000,
2002; Endo, Ikata, Katoh, & Takeda, 2001; Lin, Hanten, Olson, Roddey, Soto-quijano, Lim, et
al., 2005) while others have shown improvement (McClure, Michener, & Karduna, 2006;
McClure, Michener, Sennett, & Karduna, 2001; Laudner, Myers, Pasquale, Bradley, & Lephart,
2006) or no difference (Hebert, Moffet, McFadyen, & Dionne, 2002).

38
Table 6: Differences in scapular motion during shoulder elevation in healthy control and impact populations
Learn
Method
Example
Upward
rotation
Posterior tilt
External
rotation
Internal
rotation
Interval (°)/
plane
Commentary
Lukasiewi
cz dkk.
(1999)
Elektromec
hanical
Digitizer
20 controls
17 OLDER
BROTHERS
No
difference
↓ At 90° and
maximum
elevation
No
difference
?
0-
max/sca
pular
25-66 years male
and female
Ludewig
& Cook
(2000)
sEMG
26 controls
26 SYSTEM
↓ At 60°
altitude
↓ at 120°
↓
When
loaded
?
0-120 /
Skapular
Only males 20-71
years old, above
the head
Worker
McClure
dkk.
(2006)
sEMG
45 controls
45 SYSTEM
↑ at 90°
and 120°
in the
sagittal
plane
↑ at 120° in
the scapular
plane
No
difference
?
0-
max/scapula
r and sagittal
24-74 years old
male and female

38
Endo et
al. (2001)
Radiograf
statis
27 OLDER
BROTHERS
Bilateral
comparison
↓ At 90°
↓ at 45° and
90° elevation
No
difference
?
0-90 /
Frontal
41-73 years old
male and female
Graichen
dkk.
(2001)
Static MRI
14 Controls
20 SIS
Insignificant
difference
?
?
?
0-120 /
Frontal
22-62 years old
male female
Hebert
dkk.
(2002)
Calculated
with optical
surface
Sensor
10 Controls
41 OLDER
BROTHERS
There is no
significant
difference
s
There is no
significant
difference
?
↑ Side by
side with
SIS
0-110 /
Frontal
and
Coronal
30-60 years of
both sexes, used
bilaterally
Shoulder
Lin et al.
(2005)
sEMG
25 controls,
21 shoulder
dysfunction
↓ in the
SD
group
↓ in the SD
group
?
There is no
significant
difference
Approx. e 0-
120 /
Scapper
field
Male only, 27-
82 years old
Laudner
et al.
sEMG
11 Controls
11 Internal
Not
Significant
↑ in clash
?
Not
Significant
0-120 /
Scapper
Only men,
Pitcher, 18-30

38
(2006)
impact
differences
differences
field
years old

39
Similarly, researchers have reported a decrease in upward rotation in SAS populations
(Ludewig & Cook, 2000, 2002; Endo, Ikata, Katoh, & Takeda, 2001; Lin, Hanten, Olson, Roddey,
Soto-quijano, Lim, et al., 2005) while others have shown improvement (McClure, Michener, &
Karduna, 2006) or no difference (Lukasiewicz, McClure, Michener, Pratt, & Sennett, 1999;
Hebert, Moffet, McFadyen, & Dionne, 2002; Laudner, Myers, Pasquale, Bradley, & Lephart,
2006; Graichen, Stammberger, Bone, Wiedemann, Englmeier, Reiser, & Eckstein, 2001). Finally,
researchers have also reported a decrease in external rotation during weighted elevation (Ludewig
& Cook, 2000) while others have shown no difference during unweighted elevation (Lukasiewicz,
McClure, Michener, Pratt, & Sennett, 1999; Endo, Ikata, Katoh, & Takeda, 2001; McClure,
Michener, Sennett, & Karduna, 2001). One study has reported an increase in internal rotation
(Hebert, Moffet, McFadyen, & Dionne, 2002) while the other has shown no difference (Lin,
Hanten, Olson, Roddey, Soto-quijano, Lim, et al., 2005; Laudner, Myers, Pasquale, Bradley, &
Lephart, 2006) or reported a decline (Ludewig & Cook, 2000). Yet with all these deviations and
differences, the study seems to agree that athletes with SIS have reduced the rotation upwards
during elevation (Ludewig & Cook, 2000, 2002; Endo, Ikata, Katoh, & Takeda, 2001; Lin, Hanten,
Olson, Roddey, Soto-quijano, Lim, et al., 2005) with the exception of one study (McClure,
Michener, & Karduna, 2006).
These conflicting results in the scapula motion literature are likely due to smaller (25°-
30°) measurements of scapula tilt and internal/external rotation when compared to upward rotation
of the scapula (50°), altered scapula kinematics associated with specific types of impacts, unclear
specific muscle contributions to anterior/posterior tilt and internal/external rotation, and/or lack
of valid scapula motion measurement techniques at anterior/posterior tilt and internal/external
rotation compared to upward rotation.

40
Scapular muscles have also shown altered muscle activation patterns during increased
clash populations including increased activation of upper trapezius and decreased activation of
middle/lower trapezius and anterior serratus (Cools et al., 2007; Cools, Witvrouw, Declercq,
Danneels, & Cambier, 2003; Wadsworth & Bullock-Saxton, 1997). In contrast, Ludewig & Cook
(Ludewig & Cook, 2000), showed increased activation in the upper and lower trapezius in SIS
when compared to the control, and Lin and colleagues (Lin, et al., 2005) showed no change in the
activity of the lower trapezius These different results make the final EMG assessment unclear in
the impingement population, but there are several possible explanations for the difference in
results including: 1) Ludewig & Cook conducted an experiment there weighted on male and
female construction workers, 2) Lin and colleagues conducted their experiment with multiple
shoulder pathologies and in men only, 3) Cools and colleagues used maximum isokinetic testing
in abductions in overhead athletes, and 4) all of these studies show a large age range in their
populations.
However, there is a lack of reliable studies in the literature relating to changes in EMG
activity in overhead throwers with SIS after injury/pre-rehabilitation and after post-rehabilitation
injury. The inability of researchers to detect significant differences between groups was mainly
due to limited sample size, limited statistical power for some comparisons, large variation in
healthy populations, sEMG signals in studies altered by skin movements, and limited static
imaging on the back.
2.4.9 Abnormal glenohumeral/rotator cuff EMG activity
Abnormal muscle patterns in deltoid-rotator cuffs and/or anterior posterior rotator cuff
style pairs may contribute to SIS and have been shown in impingement populations (Myers,
Hwang, Pasquale, Blackburn, & Lephart, 2008; Reddy, Mohr, Pink, & Jobe, 2000). At

41
in general, researchers have found decreased deltoid activity (Reddy, Mohr, Pink, & Jobe, 2000),
deltoid atrophy (Leivseth & Reikeras, 1994), and decreased rotator cuff activity (Reddy, Mohr,
Pink, & Jobe, 2000) that can lead to decreased stabilization, unopposed deltoid activity, and
induce compression of subacromial structures leading to 1.7mm-2.1mm humeral head
anteriosuperior migration during 60°-90° abduction (Sharkey, Marder, & Hanson, 1994). The
impingement population has shown a decrease in EMG activity of infraspinatus and subscapularis
from an altitude of 30°-90° when compared to controls (Reddy, Mohr, Pink, & Jobe, 2000).
Myers and colleagues (Myers, Hwang, Pasquale, Blackburn, & Lephart, 2009) have
shown by fwEMG analysis, decreased rotator cuff coactivation (subscapularis- infraspinatus and
supraspinatus-infraspinatus) and abnormal deltoid activation (increase in middle deltoid
activation from 0-30°) during humerus elevation in 10 subjects with subacromial impingence
when compared to 10 healthy controls and the authors hypothesize this contributes to their
symptoms.
Isokinetic testing has also shown a lower protraction/retraction ratio in 30 overhead
athletes with chronic shoulder impingement when compared to controls (Cools, Witvrouw,
Mahieu, & Danneels, 2005). A decrease in isokinetic force output has also been shown in the
protractor muscles of overhead athletes with impact (-13.7% at 60 degrees/s; -15.5% at 180
degrees/s) (Cools, Witvrouw, Mahieu, & Danneels, 2005).
2.5 REHABILITATION CONSIDERATIONS
Current impingement treatment generally begins with conservative methods, including
arm rest, physical therapy, nonsteroidal anti-inflammatory drugs (NSAIDs), and subachromial
corticosteroid injections (de Witte, et al., 2011). Although beyond the scope of this paper,
interventions should be based on thorough and accurate clinical examination including

42
observation, posture evaluation, manual muscle testing, individual joint evaluation, functional
testing, and shoulder complex specific testing. Based on this clinical examination and stage of
healing, treatments and interventions are prescribed and, while each form of treatment is
important, this section of the paper will primarily focus on the role of prescribing specific
therapeutic exercises in rehabilitation. Also important but beyond the scope of this paper, is to
implement the proper development of exercises based on pathology, clinical examination, and
stage of healing.
Current treatments in rehabilitation aim to address the types of shoulder pathologies
involved and present dysfunction including movement compensation patterns, poor motor control,
shoulder mobility/stability, thoracic mobility, and ultimately reducing pain to return the individual
to his or her previous level of function. As our knowledge of specific muscle activity and
biomechanics has increased, the gradual development towards more scientifically based
rehabilitation exercises, which facilitate recovery while placing minimal strain on healing tissue,
has been reported in the literature (Reinold, Escamilla, & Wilk, 2009). When treating overhead
athletes with impingement, staging soft tissue lesions will have an important impact on the
prognosis for conservative treatment and overall recovery. Understanding the biomechanical
factors discussed earlier about normal shoulder function, pathological shoulder function, and the
exercises performed is necessary to safely and effectively design and prescribe the right
therapeutic exercise program.
2.5.1 Rehabilitation protocols in impact
Typical impact treatments in physical therapy clinical settings include supervised specific
exercises, manual therapy, posture education, flexibility exercises, recording, and modality
treatments and are given based on treatment phase (acute, intermediate,

43
further reinforcement, or return to sports). For the purposes of this paper, the focus is on
supervised specific exercises that refer to tackling individual muscles with therapeutic exercises
geared toward addressing strength or endurance deficits in specific muscles. Muscles that are the
focus of rehabilitation include the rotator cuff (RTC) (supraspinatus, infraspinatus, teres minor,
and subscapularus), scapular stabilizers (rhomboid major and minor, upper trapezius inferior,
lower trapezius , middle trapezius and serratus anterior), deltoids, and accessory muscles (dorsi
latisimmus, biceps brachii, coracobrachialis, pectoralis major, pectoralis minor).
Recent research has shown strengthening exercises that focus on specific muscles (serratus
anterior, trapezius, infraspinatus, supraspinatus, and teres minor) may be more beneficial for
athletes with impact and exercise recipes should be based on the EMG activity profile of the
exercise (Reinold, Escamilla, & Wilk, 2009). In order to prescribe the right exercise based on
scientific reasons, the EMG muscle activity profile of the exercise must be known and various
authors have found different results with the same exercise (See APPENDIX). Another important
component is to focus on muscles known to be dysfunctional in the shoulder span population,
specifically the inferior and middle trapezius, anterior serratus, supraspinatus, and infraspinatus.
A number of researchers have demonstrated that the 3 parts of the trapezius generally act
as a rotator and elevator up the scapular (upper trapezius), a scapula retractor (middle trapezius),
and a rotator and depressor down (lower trapezius) (Reinold, Escamilla, & Wilk, 2009). The lower
trapezius also contributes to the scapular posterior slope and external rotation during elevation,
which is hypothesized to reduce the risk of impact (Ludewig & Cook, 2000) and makes the lower
trapezius very important in rehabilitation. The EMG activity of the upper trapezius has shown a
progressive increase from 0-60°, remains constant from 60-120°, and increases

44
from 120-180° during elevation (Bagg & Forrest, 1986). In contrast, the EMG activity of the
lower trapezius tends to be low during elevation, flexion, and abduction below 90° and then
progressively increases from 90°-180° (Bagg & Forrest, 1986; Ekstrom, Donatelli, & Soderberg,
2003; Hardwick, Beebe, McDonnell, & Lang, 2006; Moseley, Jobe, Pink, Perry, & Tibone, 1992;
Smith, et al., 2006).
Several exercises have been recommended to activate the lower trapezius to the maximum
and the following exercises have shown high moderate to maximum (65-100%) contractions
including: 1) vulnerable horizontal abduction at 135° with ER (97±16% MVIC; Ekstrom,
Donatelli, & Soderberg, 2003); 2) ER stands at 90° abduction (88±51% MVIC; Myers, Pasquale,
Laudner, Sell, Bradley, & Lephart, 2005); 3) ER is vulnerable to 90° abduction (79±21% MVIC;
Ekstrom, Donatelli, & Soderberg, 2003); 4) horizontal abduction is vulnerable at 90° abduction
with ER (74±21% MVIC; Ekstrom, Donatelli, & Soderberg, 2003)(63±41%MVIC; Moseley,
Jobe, Pink, Perry, & Tibone, 1992); 5) abduction above 120° with ER (68±53% MVIC; Moseley,
Jobe, Pink, Perry, & Tibone, 1992); and 6) prone rowing (67±50% MVIC; Moseley, Jobe, Pink,
Perry, & Tibone, 1992).
Much greater EMG activity has been reported in prone ERs at 90° when compared to
empty can exercises (Ballantyne, et al., 1993) and authors have reported significant EMG
amplitudes during prone ERs at 90°, prone full cans, and vulnerable horizontal abductions at 90°
with ER (Ekstrom, Donatelli, & Soderberg, 2003). Based on these results, it appears that obtaining
maximum EMG activity from the lower trapezius in prone exercise in prone exercises around 120-
130° abduction may be most beneficial and will fluctuate depending on body type. It is also
important to note that this exercise has been performed on the stomach, not standing. Usually SIS
symptoms increase during larger standing abductions

45
from 90°, therefore this exercise is performed in the scapular plane with an external rotation of
the shoulder to clear the subacromial structures of impact on the acromion and should not be
performed during the acute phase of healing in the SIS.
It is often clinically beneficial to increase the ratio of lower trapezius and upper trapezius
in rehabilitation. Poor posture and muscle imbalance are often seen in shoulder impingements
along with changes in the force pair between the upper trapezius and the anterior serratus.
McCabe and colleagues (McCabe, Orishimo, McHugh, & Nicholas, 2007) showed that "press up"
(56% MVIC) and "scapular retraction" (40% MVIC) exercises showed significantly lower
trapezius sEMG activity than "bilateral external shoulder rotation" and "scapulas depression"
exercises. The authors also point out that "bilateral external shoulder rotation" and "upward
emphasis" show the highest UT:LT ratios at 2.35 and 2.07 (McCabe, Orishimo, McHugh, &
Nicholas, 2007). Even with the authors proposing interpretations to apply to patient populations;
It is difficult to apply the results to patients because the experiment was conducted on a healthy
population.
The central trapezius has shown high EMG activity during elevation at 90° and
>120° (Bagg & Forrest, 1986; Decker, Hintermeister, Faber, & Hawkins, 1999; Ekstrom,
Donatelli, & Soderberg, 2003), while other authors have shown low EMG activity in the same
exercise (Moseley, Jobe, Pink, Perry, & Tibone, 1992).
However, some exercises have been recommended to activate the middle trapezius to
the maximum and the following exercises have shown high moderate to maximum contractions
(65-100%) including: 1) horizontal abduction is vulnerable at 90° abduction with IR
(108±63%MVIC; Moseley, Jobe, Pink, Perry, & Tibone, 1992); 2) horizontal abduction on the
stomach at 135° abduction with ER (101±32% MVIC; Ekstrom, Donatelli, & Soderberg, 2003);

46
3) Stomach

47
horizontal abduction at 90° abduction with ER (87±20% MVIC; Ekstrom, Donatelli, & Soderberg,
2003)(96±73%MVIC; Moseley, Jobe, Pink, Perry, & Tibone, 1992); 4) prone rowing (79±23%
MVIC; Ekstrom, Donatelli, & Soderberg, 2003); and 5) supraneal extension at 90° flexion
(77±49% MVIC; Moseley, Jobe, Pink, Perry, & Tibone, 1992). In the exercise "horizontal
abduction prone to 90° abduction with ER", the authors showed some agreement in the amplitude
of EMG activity. One author showed 87±20% MVIC (Ekstrom, Donatelli, & Soderberg, 2003)
while the second showed 96±73% MVIC (Moseley, Jobe, Pink, Perry, & Tibone, 1992), while
this amplitude was not precise, both were considered maximum EMG activity.
The supraspinatus is also a very important muscle to focus on in SIS rehabilitation due to
the large number of power pairs involved and the potential for injury during SIS. Originally Jobe
(Jobe & Moynes, 1982) recommended scapular plane elevation with glenohumeral IR exercises
(empty cans) to strengthen the supraspinatus muscles, but other authors (Poppen & Walker, 1978;
Reinold, et al., 2004) have suggested scapular plane elevation with glenohumeral (full can) ER
exercises. Recently, evidence-based therapeutic exercise prescriptions have avoided the use of
empty can exercises due to increased deltoid activity potentially increasing the number of superior
humerus head migrations and the inability of weak RTCs to counteract force in impact populations
(Reinold, Escamilla, & Wilk, 2009).
Several exercises have been recommended to activate the supraspinatus to the maximum
and the following exercises have shown high moderate to maximum (65-100%) contractions
including: 1) push-ups plus (99±36% MVIC; Decker, Tokish, Ellis, Torry, & Hawkins, 2003), 2)
horizontal abductions prone to 100° abductions with ER (82±37% MVIC; Reinold et al., 2004);
3) ER is vulnerable to 90° abduction (68±33% MVIC; Reinold et al., 2004); 4)

48
military press (80±48%MVIC; Townsend, Jobe, Pink, & Perry, 1991); 5) scaption above 120° with
IR (74±33% MVIC; Townsend, Jobe, Pink, & Perry, 1991); and 6) flexion above 120° with ER
(67±14% MVIC; Townsend, Jobe, Pink, & Perry, 1991)(42±21%MVIC; Myers, Pasquale,
Laudner, Sell, Bradley, & Lephart, 2005). Interestingly, some of the same exercises showed
different results in EMG amplitude in different studies. For example, "flexion above 120° with
ER" showed 67±14% MVIC (Townsend, Jobe, Pink, & Perry, 1991) in one study and 42±21%
MVIC (Myers, Pasquale, Laudner, Sell, Bradley, & Lephart, 2005) in another. As you can see, this
is a big difference, but the potential mechanism for the difference may be due to the fact that one
study used dumbbells and the other used resistance tubes. In addition, the participants were not
weighted based on a maximum of ten repetitions.
3-D biomechanical model data imply that infraspinatus is a more effective shoulder ER at
lower abduction angles (Reinold, Escamilla, & Wilk, 2009) and many studies have tested this
model with conflicting results in exercise selection (Decker, Tokish, Ellis, Torry, & Hawkins,
2003; Myers, Pasquale, Laudner, Sell, Bradley, & Lephart, 2005; Townsend, Jobe, Pink, & Perry,
1991; Reinold, et al., 2004). In general, the activity of the minor, infraspinatus and terrace
decreases further as the shoulder moves to the abducted position while the supraspinatus and
deltoid increase activity.
Several exercises have been recommended to activate the infraspinatus to the maximum,
the following exercises have shown high moderate to maximum (65-100%) contractions
including: 1) push-ups plus (104±54% MVIC; Decker, Tokish, Ellis, Torry, & Hawkins, 2003);
2) SL ER at 0° abduction (62±13% MVIC; Reinold et al., 2004) (85±26% MVIC, Townsend,
Jobe, Pink, & Perry, 1991); 3) horizontal abduction prone to 90° abduction with ER (88±25%
MVIC; Townsend, Jobe, Pink, & Perry, 1991); 4) Horizontal Stomach

49
abduction at 90° abduction with IR (74±32% MVIC; Townsend, Jobe, Pink, & Perry, 1991); 5)
abductions above 120° with ER (74±23% MVIC; Townsend, Jobe, Pink, & Perry, 1991); and 6)
flexion above 120° with ER (66±16% MVIC; Townsend, Jobe, Pink, & Perry, 1991)
(47±34%MVIC; Myers, Pasquale, Laudner, Sell, Bradley, & Lephart, 2005).
Reinold and colleagues (Reinold, et al., 2004) also examined several exercises, commonly
used in rehabilitation, that are used to strengthen the posterior RTC and in particular the
infraspinatus and minor terraces. The authors determined that the 3 exercises showed the best
combined EMG activity and in order included: 1) side-lying ER (infraspinatus, 62% MVIC; minor
terrace, 67% MVIC); 2) ER stands in the scapular plane at 45° abduction (infraspinatus, 53%
MVIC; minor terrace, 55% MVIC); and 3) ER vulnerable to 90° abduction position (infraspinatus,
50% MVIC; minor terrace, 48% MVIC). The 90° abduction position is usually used on overhead
athletes to simulate the throwing position on overhead athletes. Side-lying ER exercises are also
clinically significant because they provide less capsular tension, specifically on the anterior band
of the glenohumeral ligament (Reinold, et al., 2004), than the more functionally advantageous
standing ER at 90°. It has also been shown that the application of a towel roll when performing
ER at 0° increases EMG activity by about 20% when compared to no towel roll (Reinold, et al.,
2004).
The anterior serratus contributes to the posterior tilt of the scapula, upward rotation, and
external rotation of the scapula (Ludewig & Cook, 2000; McClure, Michener, & Karduna, 2006)
and has shown decreased EMG activity in impact populations (Cools et al., 2007; Cools,
Witvrouw, Declercq, Danneels, & Cambier, 2003; Wadsworth & Bullock-Saxton, 1997). The
activity of the anterior serratus tends to increase as the arm elevation increases; however, increased
elevation can also increase the symptoms and risk of impact (Reinold, Escamilla, & Wilk,

50
Interestingly, performing a 90° shoulder abduction with IR or ER has resulted in high anterior
serratus activity, whereas initially Jobe (Jobe & Moynes, 1982) recommended IR or ER for the
strengthening of the rotator cuff. Anterior serratus activity also increases as gravity challenges
increase when comparing wall push ups plus, push-ups plus on the knees, and push-ups plus with
elevated legs (Reinold, Escamilla, & Wilk, 2009).
Previous authors have recommended push-up plus, dynamic hug, and punch exercises to
specifically recruit the anterior serratus (Decker, Hintermeister, Faber, & Hawkins, 1999) while
data from other authors (Ekstrom, Donatelli, & Soderberg, 2003) suggest that performing
movements that create upward rotation/protraction scapular (a stroke at 120° abduction) and
diagonal exercises that combine flexion, horizontal abduction, and ER.
Hardwick and college (Hardwick, Beebe, McDonnell, & Lang, 2006) contradict previous
authors (Ekstrom, Donatelli, & Soderberg, 2003) showing no statistical difference in anterior
serratus EMG activity during wall slides, push-ups plus (only at 90°), and scapular plane shoulder
elevation in 20 healthy individuals measured at 90°, 120°, and 140°. The study also showed that
the EMG activity of the elevation of the sliding shoulders of the wall and the scapular plane was
highest at 140° (about 76% MVIC and 82% MVIC). However, these results should be interpreted
with caution because the methodological problems of the healthy sample were limited and only
the plus phase of the push-up plus exercise was examined in this study.
The anterior serratus is important for the acceleration phase of overhead throws and several
exercises have been recommended to activate this muscle to its fullest. The following exercises
have shown high moderate to maximum (65-100%) contractions including: 1) D1 diagonal pattern
flexion, horizontal adduction, and ER (100±24% MVIC; Ekstrom, Donatelli, & Soderberg, 2003);
2) scaptions above 120° with ER (96±24% MVIC; Ekstrom, Donatelli, &

51
Soderberg, 2003)(91±52% MVIC Serratus, 84±20% MVIC Serratus Lower; Moseley, Jobe, Pink,
Perry, & Tibone, 1992); 3) supine shot up (62±19% MVIC; Ekstrom, Donatelli, & Soderberg,
2003); 4) flexion above 120° with ER (96±45% MVIC Middle Serratus, 72±46% MVIC Lower
Serratus; Moseley, Jobe, Pink, Perry, & Tibone, 1992) (67±37%MVIC; Myers, Pasquale, Laudner,
Sell, Bradley, & Lephart, 2005); 5) kidnapping above 120° with ER (96±53% MVIC Serratus,
74±65% MVIC Serratus Lower; Moseley, Jobe, Pink, Perry, & Tibone, 1992); 7) military press
(82±36% MVIC Serratus Tengah, 60±42% MVIC Serratus Lower; Moseley, Jobe, Pink, Perry, &
Tibone, 1992); 7) push-ups plus (80±38% MVIC Serratus Middle, 73±3% MVIC Serratus Lower;
Moseley, Jobe, Pink, Perry, & Tibone, 1992); 8) push-ups with separate hands (57±36% MVIC
Serratus Middle, 69±31% MVIC Serratus Lower); Moseley, Jobe, Pink, Perry, & Tibone, 1992);
9) ER stands at 90° abduction (66±39% MVIC; Myers, Pasquale, Laudner, Sell, Bradley, &
Lephart, 2005); and 10) forward standing scapular stroke (67±45% MVIC; Myers, Pasquale,
Laudner, Sell, Bradley, & Lephart, 2005).
Although studies have shown exercises that may be more beneficial than others, the lack
of statistical analysis, lack of data, and the absence of significant muscle activity (including
deltoid) are methodological limitations of this study. Also, while performing exercises with high
EMG activity is the most effective to train certain muscles to the maximum, the rehabilitation
stage can contraindicate the specific exercises recommended. For example, it is generally accepted
that performing standing exercises below 90° is necessary to avoid exacerbations of impact
symptoms. In conclusion, the therapeutic exercises described earlier have shown clinical benefits
and high EMG activity in the muscles discussed earlier (Table 5).

52
2.5.2 Rehabilitation of scapula discinesis
Scapular rehabilitation should be based on accurate and thorough clinical evaluations
conducted by licensed individuals to evaluate and treat dysfunction to enable proper goal setting
and rehabilitation for the patient. A comprehensive initial patient interview is required to ensure
the individual's functional requirements and problematic activities followed by a physical
examination. Healthcare professionals must address all possible deficiencies found at various
levels of the kinetic chain and proper treatment goals must be established that lead to appropriate
rehabilitation strategies. Therefore, although it is considered a key point in functional shoulder and
neck rehabilitation, more proximal links in kinetic chains, such as thoracic spine mobility and
strength, core stability and lower limb function, will not be discussed in this manuscript.
Treatment of scapular dyskinesis is only successful if the anatomical basis is optimal and
the individual does not present problems requiring surgery such as nerve injury, scapula muscle
detachment, severe bone disorders (achromoclavicular separation, clavicle fracture) or soft tissue
disorders (labral injury, rotator cuff disease, glenohumeral instability) (Kibler & Sciascia, 2010;
Wright, Wassinger, Frank, Michener, & Hegedus, 2012). Most cases of dyskinesis, however, are
caused by muscle weakness, inhibition or inflexibility, and can be managed with rehabilitation.
Optimal rehabilitation of scapular discinetic requires addressing all the causative factors
that can create the scanines, and then restoring the balance of muscle strength that allows for the
position and movement of the scapula. The emphasis of scapular discinesis rehabilitation should
begin proximally and end distal with the initial goal of achieving the optimal position of the
scapular function (posterior tilt, external rotation and upward elevation). The anterior serratus is

53
The external rotator is important of the scapula, and the lower trapezius is the stabilizer of the
acquired scapula position. Scapular stabilization protocols should focus on re-educating these
muscles to act as dynamic scapula stabilizers, first with the application of short lever, kinetic
chain-assisted training then progressing to long lever movements. Maximum rotator cuff strength
is achieved from scapula compression and a stable and retractable rotator cuff must be performed
after scapular control is achieved (Kibler & Sciascia, 2010). Increased impact pain when
performing open-chain cuff rotator exercises indicates incorrect protocol suppression and
rehabilitation stages. The logical development of exercises (isometric to dynamic) that focuses on
strengthening the lower trapezius and anterior serratus while minimizing the activation of the
upper trapezius has been described in the literature (Kibler & Sciascia, 2010; Kibler, Ludewig,
McClure, Michener, Bak, & Sciascia, 2013), and on the guidelines of the algorithm (Figure 3)
have been proposed that are based on the recovery of soft tissue inflexibility and maximizing
muscle performance (Cools, Struyf, De Mey, Maenhout, Castelein, & Cagnie, 2013).
Some principles guide development through algorithms with the first requirement being
the acquisition of flexibility in muscles and joints as tight muscles and joint capsules can inhibit
strength activation. Also, subsequent protocols in rehabilitation should train functional
movements in a particular pattern of exercise or activity because studies have shown maximum
scapular muscle activation when muscles are activated in a functional pattern (vs isolated) (i.e.
when muscles are activated in a specific diagonal pattern using kinetic chain sequencing) (Kibler
& Sciascia, 2010). Using these principles, many rehabilitation interventions can be considered,
but a sensible program can begin with low-weight/low-activation standing exercises (activating
scapular retractors >20% MVIC) with arms below shoulder height and progressing to prone and
lateral exercises that increase weight, but still emphasize the lower trapezius and
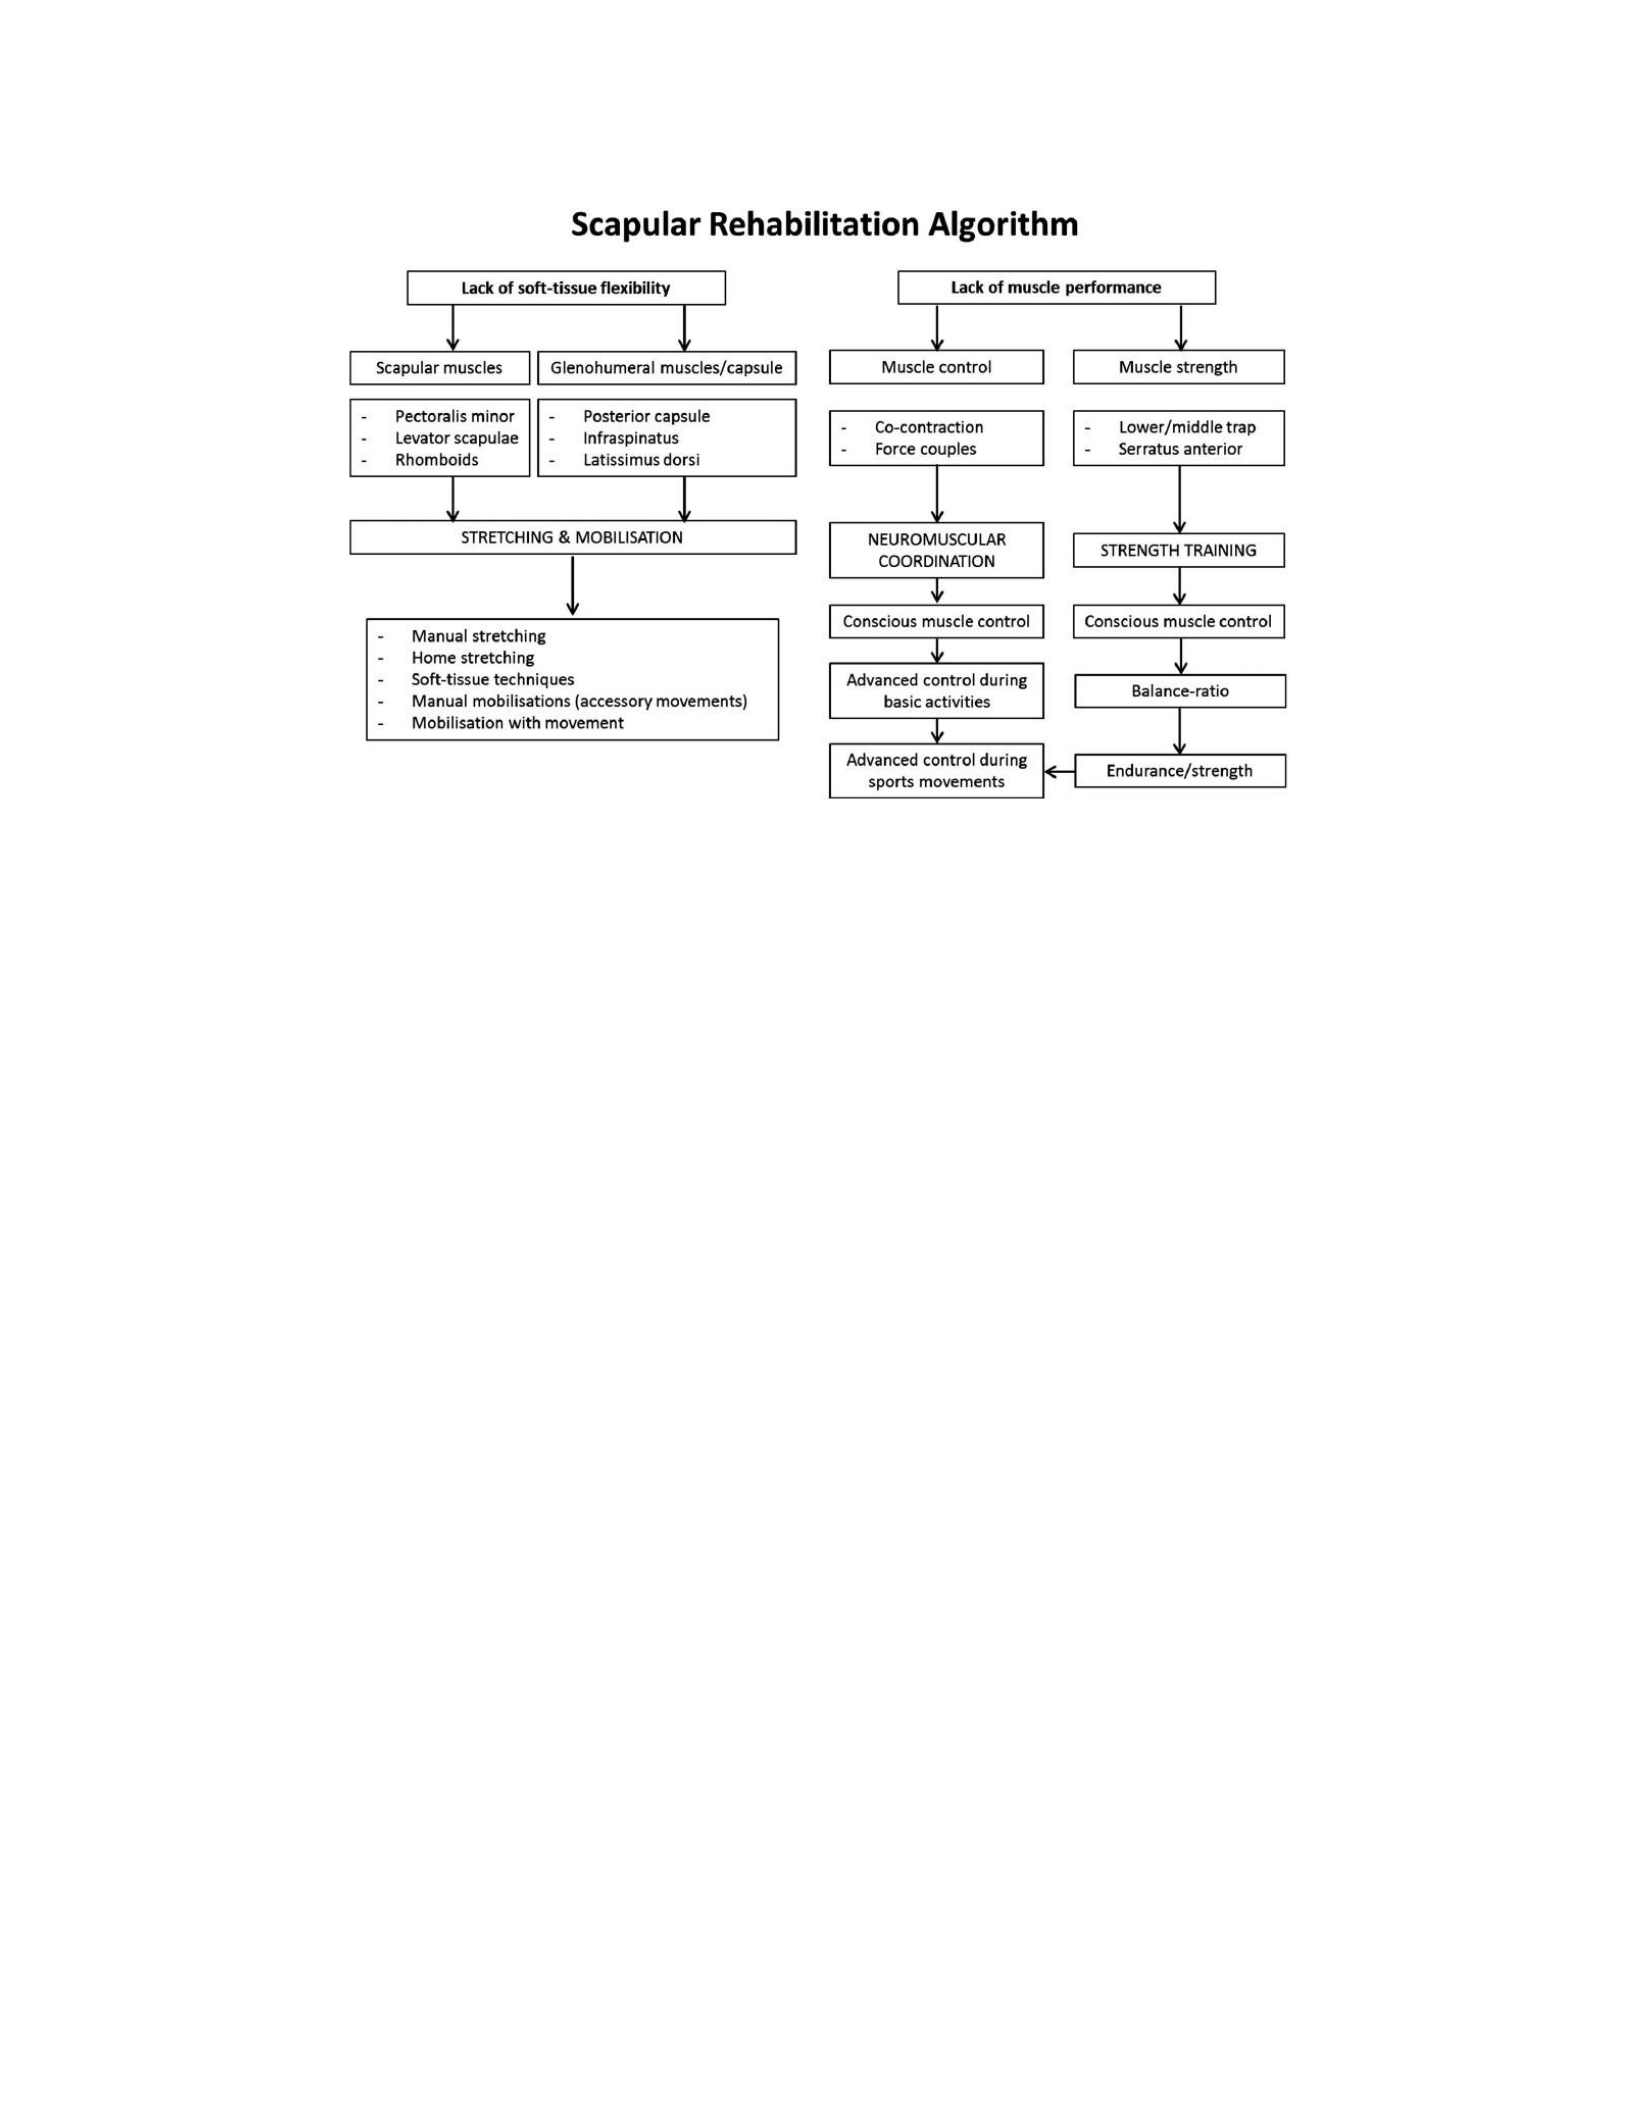
54
Figure 3: Guidelines for the scapula rehabilitation algorithm (Adapted from Cools, Struyf, De
Mey, Maenhout, Castelein, & Cagnie, 2013).
Activation of the anterior serratus over the activation of the upper trapezius. Additional load and
activation can be stimulated by integrating ipsilateral and contralateral kinetic chain activation and
adding distal resistance. Final optimization of activation can occur through weight training that
emphasizes proper retraction and stabilization. Progression can be made by increasing the
parameters of detention time, repetition, resistance, and exercise speed relevant to the patient's
functional needs.
The lower trapezius is often hampered in activation, and special efforts may be required
to 'jump start it'. Tightness, spasms and hyperactivity in the upper trapezius, pectoralis minor and
latissimus dorsi are often associated with inhibition of the lower trapezius, and specific therapy
should address these muscles.
Various studies have identified methods for activating the scapula muscles that control the

55
movement of the scapula and have identified effective body and scapular positions that allow
optimal activation to improve scapula muscle performance and reduce clinical symptoms.

56
Only two randomized clinical trials have examined the effects of a scapula-focused program by
comparing it to general shoulder rehabilitation, and the findings suggest the use of scapula
exercises results in higher patient-rated outcomes (Başkurt, Başkurt, Gelecek, & Özkan, 2011;
Struyf, Nijs, Mollekens, Jeurissen, Truijen, Mottram, & Meeusen, 2013).
Several clinical trials have included scapular exercise in their rehabilitation programs and
have found positive patient-rated outcomes in patients with impingement syndrome (Kromer,
Tautenhahn, de Bie, Staal, & Bastiaenen, 2009). It seems that not only scapula exercises but also
the inclusion of scapular exercises as part of a rehabilitation program that may include the use of
kinetic chains is the one that achieves positive results. When scapular exercises are prescribed,
several components should be emphasized, including activation sequencing, forced pair
activation, concentric/eccentric emphasis, strength, endurance and avoiding unwanted patterns
(Cools, Struyf, De Mey, Maenhout, Castelein, & Cagnie, 2013).
2.5.3 Rehabilitation effect
Conservative therapy is successful in 42% (Bigliani type III) to 91% (Bigliani type I) (de
Witte, et al., 2011) and most shoulder injuries in overhead throwers can be successfully treated
non-surgically (Wilk, Obma, Simpson, Cain, Dugas, & Andrews, 2009). Evidence supports the
use of thoracic mobilization (Theisen, et al., 2010), glenohumeral mobilization (Tyler, Nicholas,
Lee, Mullaney, & Mchugh, 2012; Sauers, 2005), strengthening of the shoulder muscles and
supervised scapula (Fleming, Seitz, & Edaugh, 2010; Osteras, Torstensen, & Osteras, 2010;
McClure, Bialker, Neff, Williams, & Karduna, 2004; Sauers, 2005; Bang & Deyle, 2000;
Senbursa, Baltaci, & Atay, 2007), supervised strengthening of the shoulder muscles and scapula
with manual therapy (Bang & Deyle, 2000; Senbursa, Baltaci, & Atay, 2007), recording (Lin,
Hung, &

57
Yang, 2011; Williams, Whatman, Hume, & Sheerin, 2012; Selkowitz, Chaney, Stuckey, & Vlad,

58
2007; Smith, Sparkes, Busse, & Enright, 2009), and laser therapy (Sauers, 2005) in reducing pain,
improving mobility, improving function, and improving changes in shoulder muscle activity.
In a systematic review of randomized controlled trials, there was a lack of high-quality
intervention studies, but few studies showed that therapeutic exercise was as effective as surgery
on SIS (Nyberg, Jonsson, & Sundelin, 2010; Trampas & Kitsios, 2006), a combination of manual
therapy and exercise is better than exercise alone in SIS (Michener, Walsworth, & Burnet, 2004),
and high-dose exercise is better than low-dose exercise in SIS (Nyberg, Jonsson, & Sundelin,
2010) in reducing pain and improving function. In evidence-based clinical practice guidelines,
therapeutic exercises are effective in the treatment of SIS (Trampas & Kitsios, 2006; Kelly,
Wrightson, & Meads, 2010) and recommended for combination with shoulder complex joint
mobilization (Tyler, Nicholas, Lee, Mullaney, & Mchugh, 2012; Sauers, 2005). Joint mobilization
techniques have shown improved symptoms when applied by experienced physical therapists
rather than by beginner physicians (Tyler, Nicholas, Lee, Mullaney, & Mchugh, 2012).
Therapeutic exercise in SIS populations has also been shown to be more beneficial than no
treatment or placebo treatment, and should be attempted to reduce symptoms and restore function
before surgical intervention is considered (Michener, Walsworth, & Burnet, 2004).
In a study by McClure and colleagues (McClure, Bialker, Neff, Williams, & Karduna,
2004), the authors showed, after a 6-week therapeutic exercise program combined with education,
significant improvements in pain, shoulder function, increased passive range of motion, increased
ER and IR forces, and no change in scapular kinematics in the SIS population.

59
However, these results must be interpreted with caution because the friction rate is 33%, there is
no control group, and many doctors intervene.
In a randomized clinical trial by Conroy & Hayes (Conroy & Hayes, 1998), 14 patients
with SIS underwent either a supervised exercise program or a supervised exercise program with
joint mobilization for 9 sessions for 3 weeks. At 3 weeks, the supervised exercise program with
joint mobilization had less pain compared to the supervised exercise program group. In a larger
randomized clinical trial by Bang & Deyle (Bang & Deyle, 2000), patients with SIS underwent a
6-session exercise program or exercise program with manual therapy for 3-4 weeks. At the end of
treatment and at 1-month follow-up, the exercise program with the manual therapy group had
superior improvements in strength, function, and pain compared to the exercise program group.
Recently, many studies have observed EMG activity in the muscles of the shoulder
complex during various rehabilitation exercises. In exploring evidence-based exercises when
treating SIS populations, the following have been shown to be effective in increasing outcome
measures for these populations: 1) serratus anterior reinforcement, 2) scapular control with
external rotation exercises, 3) external rotation exercises with tubes, 4) rejected flexion exercises,
5) rejected extension exercises, 6) rejected abduction exercises, 7) rejected internal rotation
exercises (Dewhurst, 2010).
60
Table 7: Therapeutic exercises for the shoulder muscles, involved in rehabilitation, that have shown a moderate to maximal EMG profile for a given muscle along with their
clinical significance (DB=dumbbells, T=Tubing)
Muscle
Exercise
Clinical Significance
Trapezi
u S
Lower
1. Horizontal abduction on the stomach at 135° with
ER (DB)
2. Stand ER at 90° (T)
3. Rawan Para of 90° Abd (dB)
4. Horizontal abduction prone at 90° with ER (DB)
5. Abd > 120° with ER (DB)
6. Tummy rowing (DB)
1. In line with the lower trapezius fibers, the high EMG activity of the trapezium, the effective/good anterior
supraspinatus/serratus
2. High EMG activity of lower traps, rhombuses, anterior serratus; RTC's medium-maximum EMG activity
3. Abduction below 90°; High EMG of the lower trapezius
4. Under 90° abduction, good UT:LT ratio, medium to maximum trapezius top, middle and bottom
5. Used later in rehabilitation since abduction >90° can symptoms, high serratus anterior EMG, medium upper and lower
trapezius EMG
6. Under 90° abduction, EMG high trapezius top, middle, and bottom
Trapezi
u
Middle
S
1. Horizontal abduction prone at 90° with IR (DB)
2. Horizontal abduction on the stomach at 135° with
ER (DB)
3. Horizontal abduction prone at 90° with ER (DB)
4. Tummy rowing (DB)
5. Prone extension at 90° flexion (DB)
1. IR strain on subacromial structures, deltoid activity not for patients with SIS, high EMG for all parts of the trapezius
2. High EMG activity of all parts of the trapezius is effective and good for the supraspinatus and anterior serratus as well
3. Under 90° abduction, good UT:LT ratio, medium to maximum trapezius top, middle and bottom
4. Under 90° abduction, EMG high trapezius top, middle, and bottom
5. Under 90° abduction, Medium high trapezius activity
61
Serratu
s
anterior
1. D1 diagonal pattern flexion, horizontal adduction,
and ER (T)
2. Scaption above 120° with ER (DB)
3. Supine shot up (DB)
4. Flexion above 120° with ER (DB)
5. Abduction above 120° with ER (DB)
6. Military press (DB)
7. Push-up Plus
8. Push-ups with separate hands
9. Stand ER at 90° abduction (T)
10. Forward standing scapular punch (T)
1. Effective for initiating functional movement patterns later in rehabilitation, high EMG activity
2. Above 90° which will be done after symptoms have recovered
3. Effective and below 90°
4. Above 90° which will be done after symptoms have recovered
5. Used later in rehabilitation since abduction >90° can symptoms, high serratus anterior EMG, medium upper and lower
trapezius EMG
6. Do it in the advanced strengthening phase as it can cause an impact
7. Closed chain exercises below 90°, high anterior, supraspinatus, and infraspinatus serratus activity
8. Closed chain drill
9. EMG activity of high minor terraces, low trapezius and rhombus
10. Below 90° abduction, high subscapularis and EMG activity minor terrace
suprasp
inatus
1. Push-up plus
2. Horizontal abduction prone at 100° with ER (DB)
3. Rawan Para of 90° Abd (dB)
4. Military press (DB)
5. Scaption above 120° with IR (DB)
6. Flexion above 120° with ER (DB)
1. Closed chain exercises below 90°, high anterior, supraspinatus, and infraspinatus serratus activity
2. High supraspinatus EMG activity, mid/posterior deltoid
3. Abduction below 90°; High EMG of the lower trapezius as well
4. Do it in the advanced strengthening phase as it can cause an impact
5. IR strain on subacromial structures, anterior/middle deltoid activity not for patients with moderate infraspinatus EMG
activity SIS
6. High anterior/middle deltoid activity is not for patients with SIS activity, moderate infraspinatus and subscapularis EMG

62
Table 7: Therapeutic exercises for the shoulder muscles, which are involved in rehabilitation, which have shown a moderate to maximal EMG profile for a particular
muscles along with their clinical significance (DB = dumbbells, T = Tubing) (Continued)
Muscle
Exercise
Clinical Significance
Infraspi
natus
1. Push-up plus
2. SL ER at 0° (DB) abduction
3. Horizontal abduction prone at 90° with ER (DB)
4. Horizontal abduction prone at 90° with IR (DB)
5. 120° > kidnapping with ER (DB)
6. Flexion above 120° with ER (DB)
1. Closed chain exercises below 90°, high anterior, supraspinatus, and infraspinatus serratus activity
2. Stable shoulder position; The most effective exercises to recruit infraspinatus
3. Under 90° abduction, good UT:LT ratio, medium to maximum trapezius top, middle and bottom
4. IR increases tension on subacromial structures, increased deltoid activity not for patients with SIS, high EMG for all parts
of the trapezius
5. Used later in rehabilitation since abduction >90° can improve symptoms, high anterior serratus EMG, moderate upper and
lower trapezius EMG
6. High anterior/middle deltoid activity is not for patients with SIS activity, moderate infraspinatus and subscapularis EMG
Infraspi
natus &
Teres
Small
1. SL ER at 0° (DB) abduction
2. Standing ER in scapular plane at 45° abduction
(DB)
3. ER vulnerable in 90° abduction (DB)
1. Stable shoulder position; The most effective exercises to recruit infraspinatus
2. High EMG terrace and infraspinatus
3. Abduction below 90°; High EMG of the lower trapezius

63
However, there are no studies exploring whether specific rehabilitation exercises that
target the muscles, based on the EMG profile, can correct previous EMG deficits and accelerate
recovery in patients with shoulder impingements. In conclusion, there is a need for further well-
defined clinical trials on specific exercise interventions for the treatment of SIS. The literature
reveals the need for increased sample size, better diagnostic criteria and similar diagnostic criteria
applied among studies, longer follow-ups, studies measuring function and pain, and (particularly
in overhead athletes) faster return to play.
2.6 SUMMARY
Athletes above the head with SIS or shoulder impingement will show muscle imbalance
and strain on the GH and scapular muscles. This dysfunction can lead to changes in the complex
kinematics of the shoulder, changes in EMG activity, and functional limitations, which will lead
to impingement. The exact mechanism of impact is debated in the literature as well as its
relationship to scapular kinematic variations. Therapeutic exercises have been shown to be
beneficial in reducing dysfunction and pain in SIS, and exercises supervised with manual
techniques by an experienced physician are effective treatments. It is unknown whether
prescribing specific therapeutic exercises based on the EMG profile will speed up recovery time,
improve force production, address scapular dyskinesis, or change the elevation of SAS in SIS.
Several research articles have examined these variables and their relationship with prescribing
specific therapeutic exercises and there is a general need for further well-defined clinical trials on
specific exercise interventions for the treatment of SIS.

64
CHAPTER 3: EFFECTS OF VARIOUS POSTURES ON ELECTROMYGRAPHIC
ANALYSIS OF THE LOWER TRAPEZIUS SURFACE DURING SPECIFIC
THERAPEUTIC EXERCISES
3.1 INTRODUCTION
Individuals diagnosed with shoulder impingement show muscle imbalances in the shoulder
complex and in particular in pairs of forces (lower trapezius, upper trapezius and anterior serratus),
which control the movement of the scapulas. Deltoids play an important role in muscle strength
pairs as they are the main drivers of the glenohumeral joint. Dysfunction in these muscles leads to
complex kinematic changes in the shoulder and functional limitations, which will lead to an
increase in impingement symptoms. Therapeutic exercises are beneficial in reducing dysfunction
and pain in individuals diagnosed with shoulder impingement. However, no studies have shown
the effects of various postures on electromyography activity (EMG) in healthy adults or in adults
with impact during certain therapeutic exercises. The purpose of this study was to identify the
therapeutic exercises and postures that elicited the highest EMG activity in the lower trapezius
shoulder muscles tested. The study also tested exercises and posture in healthy populations and
shoulder impingement populations because very few studies correlated specific therapeutic
exercises in shoulder impingement populations.
Individuals with shoulder impingement exhibit muscular imbalances in the shoulder
complex and specifically in the lower trapezius, upper trapezius, and anterior serratus, all of which
control the movement of the scapula, with the deltoid acting as the main driver of the shoulder.
Dysfunction in these muscles leads to kinematic changes and functional limitations,
leading to an increase in impingement symptoms. Therapeutic exercises have been shown to be
beneficial in reducing dysfunction and pain in impact and the following exercises have been shown

65
to be effective treatments for increasing the outcome measures for this diagnosis: 1) gerratus

66
Anterior reinforcement, 2) scapular control with external rotation exercises, 3) external rotation
exercises, 4) prone extension, 5) press up exercises, 6) bilateral shoulder external rotation
exercises, and 7) horizontal abduction exercises on the prone at 135° and 90° abduction
(Dewhurst, 2010; Trampas & Kitsios, 2006; Kelly, Wrightson, & Meads, 2010; Fleming, Seitz,
& Edaugh, 2010; Osteras, Torstensen, & Osteras, 2010; McClure, Bialker, Neff, Williams, &
Karduna, 2004; Sauers, 2005;; Senbursa, Baltaci, & Atay, 2007; Bang & Deyle, 2000; Senbursa,
Baltaci, & Atay, 2007). The therapeutic exercises in this study are derived from specific
therapeutic exercises that have been shown to improve outcomes in clash populations and what
is very important is the amount of EMG activity in the lower trapezius because these muscles are
directly responsible for stabilizing the scapula.
Evidence-based treatment of concussions requires high-dose therapeutic exercises with
low doses (Nyberg, Jonsson, & Sundelin, 2010) and applying exercise EMG profiles to exercise
prescriptions facilitates rapid recovery. However, there are no studies that correlate the effects of
various postures on lower trapezius EMG activity in healthy adults or in adults with impact. The
purpose of this study was to identify the therapeutic exercises and postures that elicit the highest
EMG activity in the lower trapezius muscles. Postures included in this study include normal
posture with a towel roll under the arms (if applicable), posture with staggered legs/scapula pulled
and towel rolls under the arms (if any), and normal posture/scapula pulled with a towel roll under
the arms (if any) with a physical therapist observing and gesturing to maintain scapula retraction.
Recent research has shown that the application of towel rolls increases the EMG activity of the
shoulder muscles by 20% in certain exercises (Reinold, Wilk, Fleisig, Zheng, Barrentine,
Chmielewski, Cody, Jameson, & Andrews, 2004) thereby increasing the effectiveness of
therapeutic exercises.

67
However, no studies have examined the effects of towel rolls in relation to different postures
or the effects of physical therapists observing movements and issuing verbal and tactile cues.
The study addresses two current issues. First, it sought to show whether it was more
beneficial to change posture to facilitate increased activity of the lower trapezius in healthy
individuals or individuals diagnosed with shoulder impingement. Second, it tries to provide more
clarity on which therapeutic exercises show the highest percentage of EMG activity in healthy and
pathological populations. Because physical therapists use therapeutic exercises to target specific
weak muscles, this study will be more helpful in determining which exercises chosen help activate
the target muscles to the maximum, and allow for better exercise selection and, although unknown
in the study, faster recovery times for individuals with shoulder impingements.
3.2 METHOD
One of the researchers conducted an assessment for inclusion and exclusion criteria
through the use of verbal questionnaires. The inclusion criteria for all subjects are: 1) be 18-50
years old, and 2) be able to communicate in English. Exclusion criteria for the healthy adult group
(phase 1) include: 1) a recent history (less than 1 year) of musculoskeletal injury, condition, or
surgery involving the upper extremities or cervical spine, and 2) a previous history of
neuromuscular conditions, pathologies, or numbness or tingling in both upper extremities.
Inclusion criteria for the adult impingement group (phase 2) include: 1) a recent diagnosis of
shoulder impingement by a physician, 2) a diagnosis confirmed by a physical therapist (based on
having at least 4 of the following 7 criteria): 1) Neer's stretch mark, 2) Hawkins' sign, 3) empty or
full positive can test, 4) pain with active shoulder elevation, 5) pain with palpation
68
rotator cuff tendon, 6) pain with isometric rejection abduction, and 7) pain in the dermatome region
C5 or C6 (Table 8).
Table 8: Description of inclusion criteria for adult impact group (phase 2)
Criterion
Description
Neer's impact signs
It is the reproduction of pain when the examiner passively flexes
the humerus, or shoulder, to the final range of motion and applies
Excess pressure
Hawkins sign
It is a reproduction of pain when the shoulder is placed passively
in 90° forward flexion and rotated internally to the tip
Range of motion
positive test for empty or full
cans
pain with forward flexion rejected at 90° either with the thumb
pointing up (full can) or thumb pointing down (empty can)
pain with active shoulder
Elevation
pain during active shoulder elevation or abduction of the shoulder
from
0-180 degree
pain with palpation
tendon manset rotator
pain with palpation of the shoulder muscles including
supraspinatus, infraspinatus, teres minor, dan subscapularus
pain with isometric rejected
abduction
pain with a manual muscle test in which a downward force is placed
on the shoulder at the wrist while the shoulder is in a 90-degree
abduction and the elbow is extended
pain in the area of dermatome
C5 or C6
Dermatomes C5 and C6 are located from the front and back of the
shoulder to the wrist and hand, dermatoms correlate with the nerve
root level with the location of the pain, so because the rotator cuff

69
is involved, the dermatoms will be present
with pain including dermatomes C5, C6 because the rotator cuff
is innervated by that nerve root
Exclusion criteria from the adult impact group include: 1) diagnosis and/or confirmation
of MRI of complete rotator cuff tear, 2) signs of acute inflammation including severe resting pain
or severe pain with resisted isometric abduction, 3) subjects who have prior spine-related
symptoms or are assessed to have spine-related symptoms, 4) glenohumeral instability (as
determined by a positive capture test, anterior drawers, and sulcus markings; (Table 9), and 5)
previous shoulder surgery. Subjects are also excluded if they show contraindications to exercise
(Table 10).
The study was explained to all subjects and they signed an agreement of approval approved by
the Louisiana State University institutional review board. Filtered subjects
70
Table 9: Glenohumeral instability test used in adult impact group exclusion criteria
Test
Procedure
Catch Test
Reproduction of pain when an anteriorly directed force is applied to the proximal
humerus in the 90° abduction and 90° external positions
rotation
anterior laci
The subject is supine and the examiner stands facing the affected shoulder and
holds it at 80-120° abduction, 0-20° forward flexion and 0-30° external rotation.
The examiner holds the patient's scapula spine forward with his index and
middle fingers; the thumb exerts back pressure on the koracoid. The examiner
uses his right hand to grasp the patient's relaxed upper arm and pull it forward
with force. The relative movement between the fixed scapula and the movable
humerus is valued and assessed. The click that is heard on the forward
movement of the head of the humerus due to labral pathology is positive
sign
Sulkus sign
With the subject seated, the elbows are clenched and inferior traction is applied,
the area adjacent to the acromion is observed and if the dimples are on the skin
present, then a sign of positive sulkus is present
Table 10: Contraindications to exercise

71
1.
recent changes in resting ECG indicating significant ischemia
2.
recent myocardial infarction (within 7 days),
3.
Acute cardiac events
4.
Unstable angina
5.
Uncontrolled cardiac dysrhythmia
6.
stenosis aorta parah simtomatik
7.
uncontrolled symptomatic heart failure
8.
acute pulmonary embolism or pulmonary infarction
9.
acute myocarditis or pericarditis
10.
suspected or known to have aneurysm surgery
11.
Acute systemic infection is accompanied by fever, body pain,
or swollen lymph nodes.
for latex allergy or current pregnancy. Pregnant individuals were excluded from the study and
individuals with latex allergies used a latex-free version of the resistance band.
Phase 1 participants are recruited from college students, pre-physical therapy students,
and healthy individuals who are willing to volunteer. Phase 2 participants are recruited from
current physical therapy patients who are willing to volunteer who are diagnosed by a physician
with shoulder impingement and referred to physical therapy for treatment. Participants fill out
informed consent, PAR-Q, HIPAA AUTHORIZATION AGREEMENT, and screen entries and

72
Exclusion criteria through the use of verbal questionnaires. Each phase participant was
randomized into one of three posture groups, blinded to the expected/hypothesized results of the
study, and all exercises were balanced.
Surface electrodes were applied and recorded the activity of the lower trapezius EMG
during exercise and a variety of postures in 30 healthy adults and 16 adults with impact. Healthy
subjects (phase 1) were randomized into one of three groups and performed ten repetitions on
each of the seven exercises. Subjects with impact (Phase 2) were randomly assigned to one of
three groups and performed ten repetitions on each of the same exercises.
Generally selected therapeutic exercises in the rehabilitation of individuals diagnosed with
shoulder impingement and each subject performed ten repetitions of each exercise (Table 11) with
a metronome-regulated repetition rate of up to sixty beats per minute (bpm). The subject performs
each concentric or eccentric phase of the exercise for 2 metronome beats. The determination of
mass is based on a standardized formula based on anthropometry and calculates the desired weight
from the height measurements, arm length, and weight.
On the day of the test, subjects were informed of their rights, procedures for participating
in the study, read and sign informed consents, read and sign the HIPPA authorization, discuss
inclusion and exclusion criteria with the tester, receive a brief screening check, and be oriented to
the testing protocol. The protocols are ordered as follows: randomization, determination of a
maximum of 10 repetitions, electrode placement, exercise and habituation, MVIC testing, five-
minute rest, and exercise testing. In total, the study took an hour of individual time. Phase 1
participants (healthy adult subjects) were randomized into 1 of three groups (Table 11). Group 1
consists of special therapeutic exercises carried out with

73
Table 11: Description of Specific Therapeutic Exercises and EMG activation
Group 1 (Control group, no
change of posture):
1.
Horizontal abduction prone
to 90° abduction
2.
Horizontal abduction on the
stomach at 130° abduction
3.
Sideways external rotation
4.
Prone extension 5.
External rotation of bilateral
shoulders
6.
ER prone at 90° abduction
7.
Prone paddling
1. The subject is positioned on his stomach with his shoulders resting on a 90° forward flexion. From this position, the subject abducts the arm
horizontally while maintaining the shoulder at a 90° abduction with the shoulder in an external rotation (thumb up) until the arm reaches the frontal
plane. (without conscious correction,)
2. The subject is positioned on his stomach with his shoulders resting on a 90° forward flexion. From this position, the subject abducts the arm
horizontally while maintaining the shoulder at 130° abduction with the shoulder in an external rotation (thumb up) until the arm reaches the frontal
plane. (without conscious correction,)
3. The subject lies on his side with his arms at his sides with a towel between his elbows and ribs. The subject then externally rotates the shoulder up to
50 degrees above the horizontal then returns to the resting position.
4. The subject is positioned on his stomach with his arms resting on a 90° forward flexion. The subject then extends the shoulders while keeping
the hands in supination (thumb pointing outwards) until the arms reach 5 degrees past the frontal plane then return to the resting position.
5. The subject stands with a tight elastic band in the subject's hand with the palms facing each other. The subject then bilaterally externally rotates the
shoulders while maintaining the shoulder and elbow positions past 50 degrees from the sagittal plane and then returns to the resting position.
6. The subject lies on his stomach with his shoulders in a 90° abduction and his elbows in a 90° flexion of a slight supination of the hands (thumbs
up). The subject then lifts the arm off the mattress as a whole, clears the ulna and humerus from the mattress, and then returns to the resting position.
(without conscious correction,)
7. The subject lies on his stomach with his arms resting on flexion 90° forward and his hands in supination (thumb facing sideways). The subject then
extends his shoulders and flexes his elbows simultaneously until his hands are parallel to the body. The subject then returns to the resting position.

74
Group 2 exercises include (Group
staggered legs):
1.
Horizontal abduction stands at
90° abduction
2.
Horizontal abduction stands at
130° abduction
3.
External rotation stand
4.
Extension stand 5.
External rotation of bilateral
shoulders
6.
Standing in the ER at 90°
abduction
7.
Paddle stand
1. The subject is positioned standing with his shoulders resting on a 90° flexion forward and holding an elastic band. From this position, the subject
abducts the arm horizontally while maintaining the shoulder at a 90° abduction with the shoulder in an external rotation (thumb up) until the arm
reaches the frontal plane. When performing this exercise, a therapist will initially verbally and tactilely signal the subject to stand in a staggered leg
posture with the ipsilateral leg (relative to the test shoulder) placed 1 foot long posterior to the midline and maintain constant scapular pressure while
performing the exercise (staggered posture,
2. The subject is positioned standing with his shoulders resting on flexion 90° forward. From this position, the subject abducts the arm horizontally
while maintaining the shoulder at 130° abduction with the shoulder in an external rotation (thumb up) until the arm reaches the frontal plane. When
performing this exercise, the therapist will initially verbally and tactilely signal the subject to stand in a staggered posture with the ipsilateral leg
(relative to the test shoulder) placed 1 posterior long leg to the midline and maintain constant scapular pressure while performing the exercise
(staggered posture,).
3. The subject stands with his arms at his sides with a towel between his elbows and ribs. The subject then externally rotates the shoulder up to 50
degrees above the horizontal then returns to the resting position. When performing this exercise, the therapist will initially verbally and tactilely
signal the subject to stand in a staggered posture with the ipsilateral leg (relative to the test shoulder) placed 1 posterior long leg to the midline and
maintain constant scapular pressure while performing the exercise (staggered posture).

75
Table 11: Description of Specific Therapeutic Exercises and EMG activation (advanced 1)
4. The subject is positioned standing with the arms resting on a 90° forward flexion. The subject then extends the shoulders while keeping the hands
in supination (thumb pointing outwards) until the arms reach 5 degrees past the frontal plane then return to the resting position. When performing
this exercise, the therapist will initially verbally and tactilely signal the subject to stand in a staggered posture with the ipsilateral leg (relative to the
test shoulder) placed 1 posterior long leg to the midline and maintain constant scapular pressure while performing the exercise (staggered posture,).
5. The subject stands with a tight elastic band in the subject's hand with the palms facing each other. The subject then bilaterally externally rotates the
shoulders while maintaining the shoulder and elbow positions past 50 degrees from the sagittal plane and then returns to the resting position. When
performing this exercise, the therapist will initially verbally and tactilely signal the subject to stand in a staggered posture with the ipsilateral leg
(relative to the test shoulder) placed 1 posterior long leg to the midline and maintain constant scapular pressure while performing the exercise
(staggered posture,).
6. The subject stands with the shoulders in the 90° abduction and the elbows in the 90° flexion of the hands slightly supinated (thumbs up). The subject
then extends his arms, clears the frontal plane, and then returns to the resting position. When performing this exercise, the therapist will initially
verbally and tactilely signal the subject to stand in a staggered posture with the ipsilateral leg (relative to the test shoulder) placed 1 posterior long
leg to the midline and maintain constant scapular pressure while performing the exercise (staggered posture).
7. The subject stands with the arms resting on a 90° forward flexion and the hands in supination (thumb facing sideways). The subject then extends his
shoulders and flexes his elbows simultaneously until his hands are parallel to the body. The subject then returns to the resting position. When

76
performing this exercise, a therapist will initially verbally and tactilely signal the subject to stand in a staggered posture with the ipsilateral leg
(relative to the test shoulder) placed 1 foot long posterior to the midline and maintain constant scapular pressure while performing the exercise
(staggered
posture,).
Group 3 exercises include
(Conscious correction group):
1.
Horizontal abduction prone
to 90° abduction
2.
Horizontal abduction on the
stomach at 130° abduction
3.
Sideways external rotation
1. The subject is positioned on his stomach with his shoulders resting on a 90° forward flexion. From this position, the subject abducts the arm
horizontally while maintaining the shoulder at a 90° abduction with the shoulder in an external rotation (thumb up) until the arm reaches the frontal
plane. When performing this exercise, a therapist will verbally and tactile signal the subject to contract a lower trapezius (conscious correction).
2. The subject is positioned on his stomach with his shoulders resting on a 90° forward flexion. From this position, the subject abducts the arm
horizontally while maintaining the shoulder at 130° abduction with the shoulder in an external rotation (thumb up) until the arm reaches the frontal
plane. When performing this exercise, a therapist will verbally and tactile signal the subject to contract a lower trapezius (conscious correction).
3. The subject lies on his side with his arms at his sides with a towel between his elbows and ribs. The subject then externally rotates the shoulder up to

77
4.
Prone extension 5.
External rotation of bilateral
shoulders
6.
ER prone at 90° abduction
7.
Prone paddling
50 degrees above the horizontal then returns to the resting position. When performing this exercise, a therapist will verbally and tactile signal the
subject to contract a lower trapezius (conscious correction).
4. The subject is positioned on his stomach with his arms resting on a 90° forward flexion. The subject then extends the shoulders while keeping the
hands in supination (thumb pointing outwards) until the arms reach 5 degrees past the frontal plane then return to the resting position. When
performing this exercise, a therapist will verbally and tactilely signal the subject to contract the lower trapezius (conscious correction,).

78
Table 11: Description of Specific Therapeutic Exercises and EMG activation (advanced 2)
5. The subject stands with a tight elastic band in the subject's hand with the palms facing each other. The subject then bilaterally externally rotates the
shoulders while maintaining the shoulder and elbow positions past 50 degrees from the sagittal plane and then returns to the resting position. When
performing this exercise, a therapist will verbally and tactilely signal the subject to contract the lower trapezius (conscious correction,).
6. The subject lies on his stomach with his shoulders in a 90° abduction and his elbows in a 90° flexion of a slight supination of the hands (thumbs
up). The subject then lifts the arm off the mattress as a whole, clears the ulna and humerus from the mattress, and then returns to the resting position.
When performing this exercise, a therapist will verbally and tactile signal the subject to contract a lower trapezius (conscious correction).
7. The subject lies on his stomach with his arms resting on flexion 90° forward and his hands in supination (thumb facing sideways). The subject then
extends his shoulders and flexes his elbows simultaneously until his hands are parallel to the body. The subject then returns to the resting position.
When performing this exercise, a therapist will verbally and tactilely signal the subject to contract the lower trapezius (conscious correction,).

79
normal posture without conscious correction or staggered leg posture. Group 2 performs a special
therapeutic exercise with a staggered leg posture in which the ipsilateral leg to the arm performing
the exercise is placed behind the frontal plane. Group 3 consisted of special therapeutic exercises
performed with conscious posture correction by a physical therapist.
Phase 2 of the study involved individuals who had been diagnosed with shoulder impingement
and met inclusion and exclusion criteria. Then each subject in phase 2 was randomized into one
of the three groups described above and shown in Table 11.
Group 1 exercises included (Control group, posture unchanged): 1) horizontal abduction
on the stomach at 90° abduction, 2) horizontal abduction on the stomach at 130° abduction, 3)
lateral rotation, 4) prone extension, 5) bilateral external rotation of the shoulders, 6) external
rotation of the prone at 90° abduction, and 7) prone rowing. Exercises for Group 2 include (Group
staggered legs): 1) horizontal abduction stand at 90° abduction, 2) horizontal abduction stand at
130° abduction, 3) standing, external rotation standing, 4) extension standing, 5) external rotation
of bilateral shoulders, 6) standing external rotation at 90° abduction, and 7) standing rowing. The
exercises carried out by Group 3 are (Conscious correction group): 1) horizontal abduction prone
to 90° abduction, 2) prone horizontal abduction to 130° abduction, 3) lateral lateral rotation,
4) prone extension, 5) bilateral shoulder external rotation, 6) prone external rotation at 90°
abduction, 7) prone paddling (Table 11).
Phase 1 participants included 30 healthy adults (12 men and 18 women) with an average
height of 59.6 inches (range 52 to 72 inches), an average weight of 149.37 pounds (range 115 to
220 pounds), and an average of 22.57 years (range 18-49 years). In phase 2, participants included
16 adults diagnosed with a stretch and had an average height of 65.3 inches (range 58 to 70 inches),
an average weight of 182.31 pounds (range 129 to 290 pounds), an average
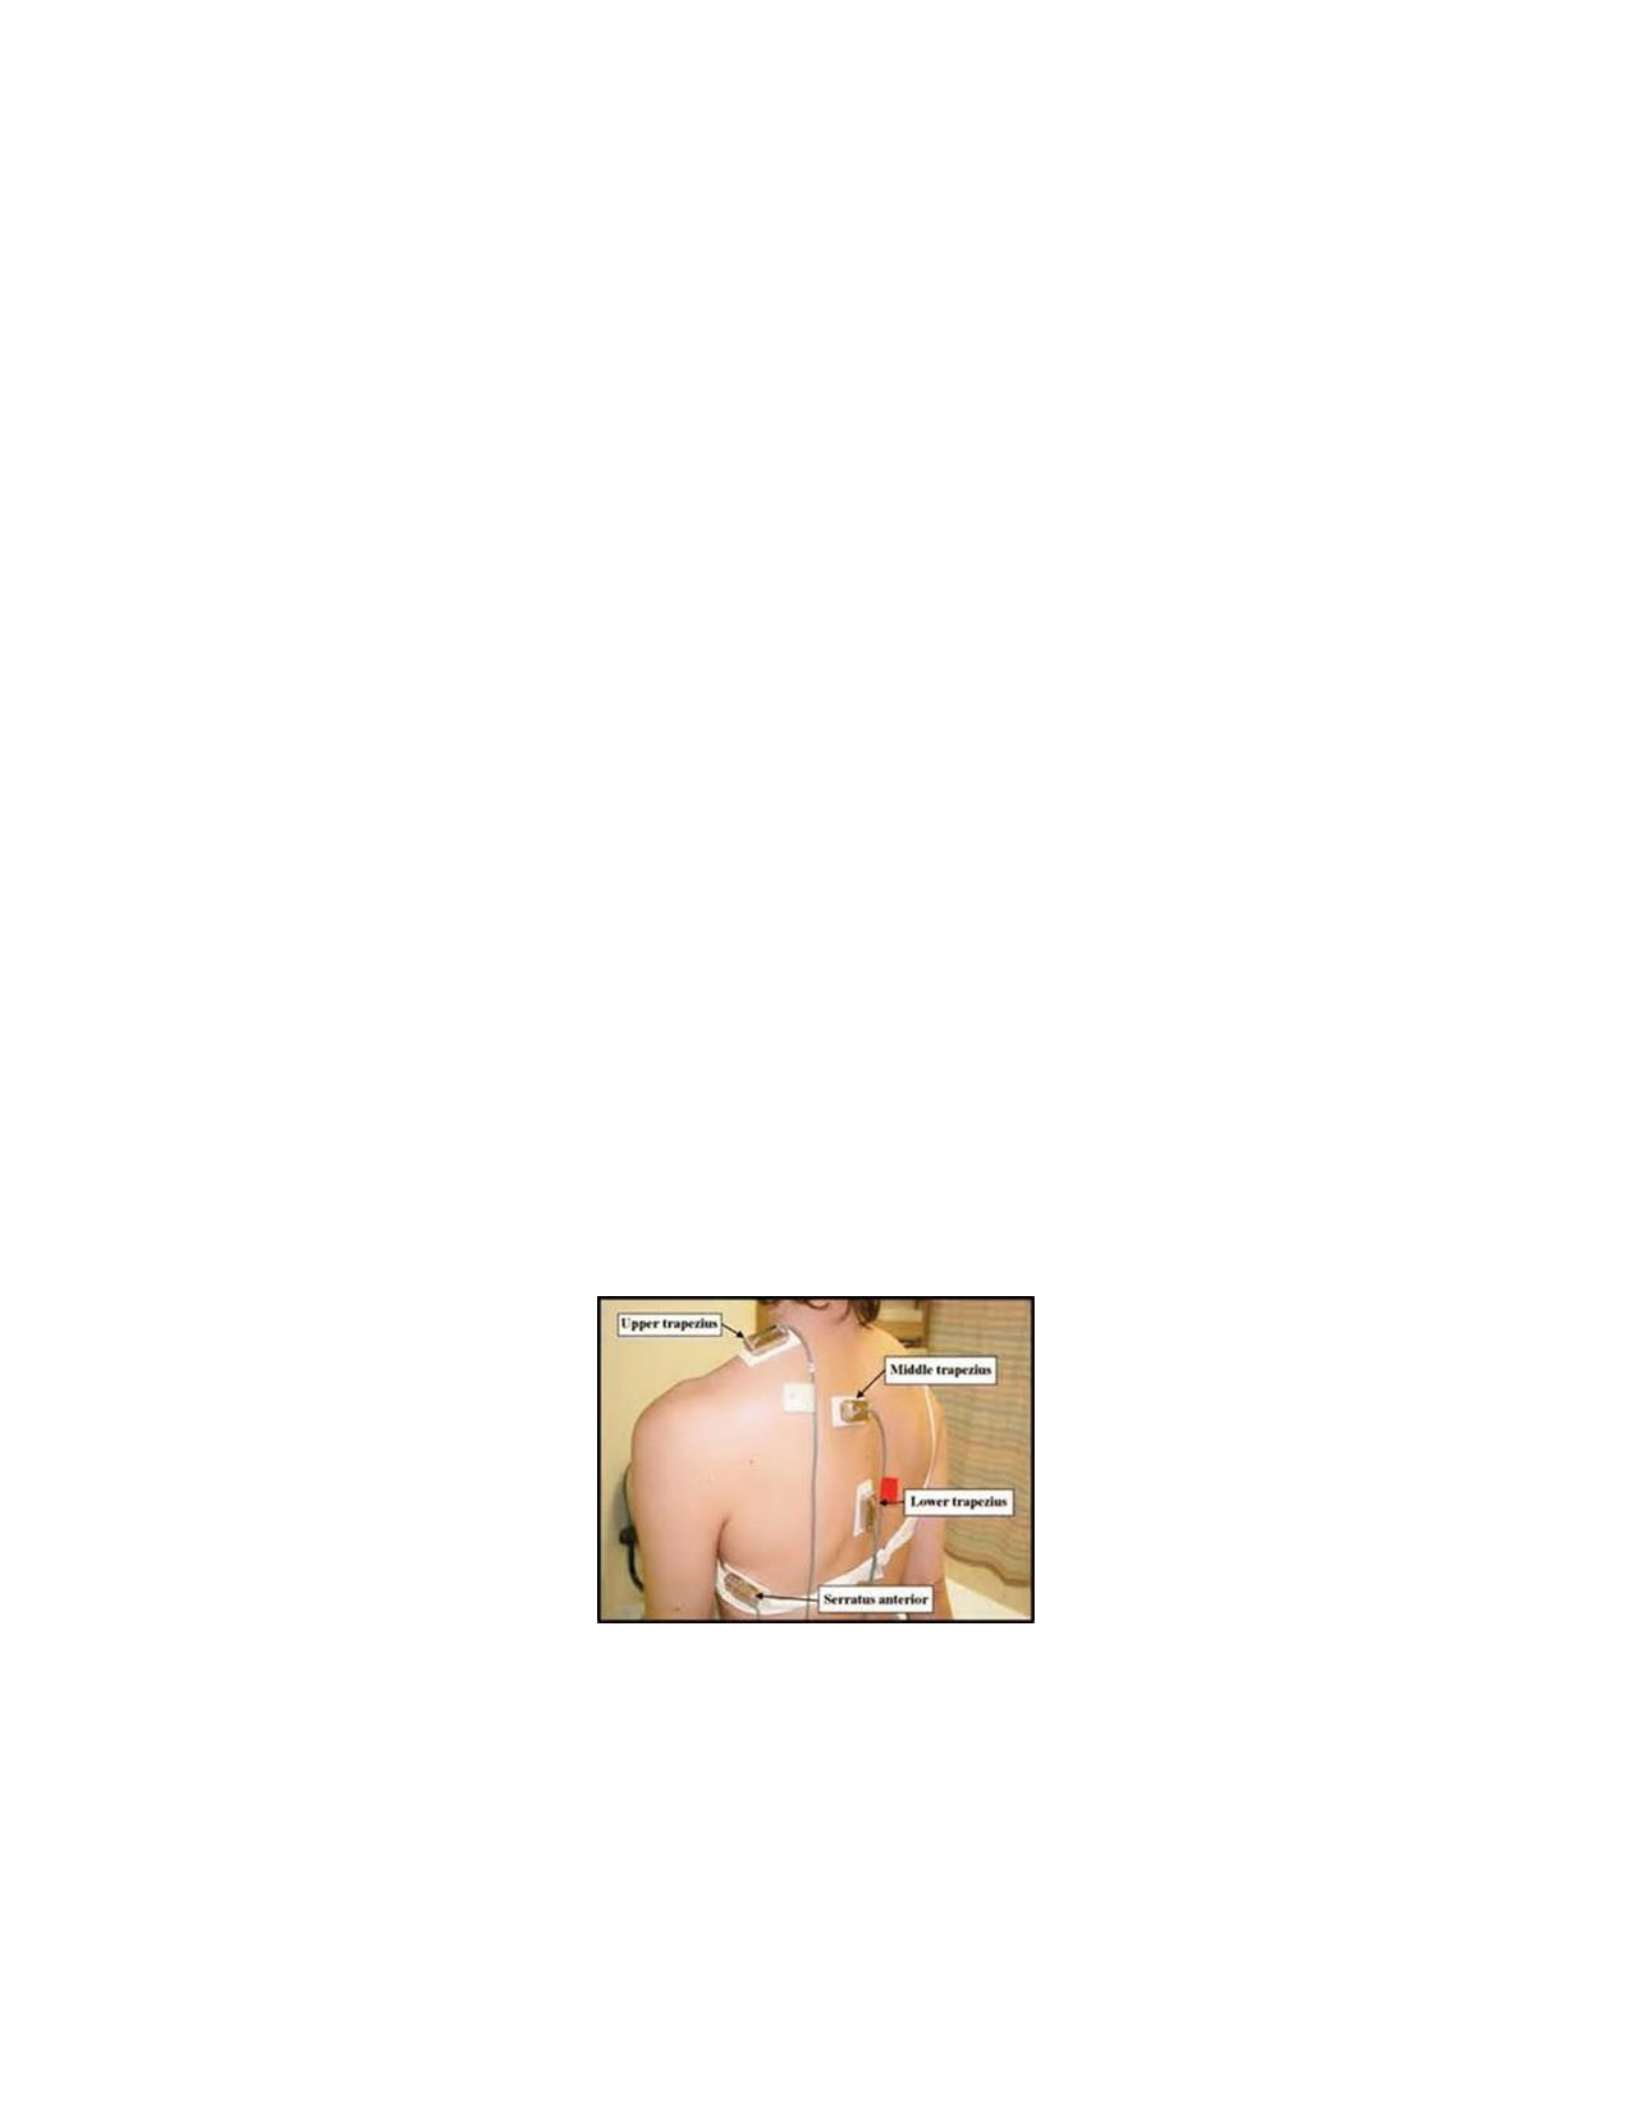
80
age 47.44 years (range 19-65 years), and average duration of symptoms 12.81 months (range 20
days to 10 years).
Muscle activity was measured in the dominant sub-shoulder trapezius muscle using
surface electromyography (sEMG). The bipolar surface electrode of Noraxon Ag-AgCl (Noraxon,
Arizona, USA) is placed over the lower trapezius abdomen using a published placement
(Basmajian & DeLuca, 1995). The position of the lower trapezius electrode is placed obliquely
upwards and laterally along the line between the junction of the scapula spine with the boundary
of the scapula vertebrae and the seventh thoracic spinosus process (Figure 4).
Prior to electrode placement, the placement area is shaved and cleaned with alcohol to minimize
impedance with the ground electrode placed over the clavicle. EMG signals were collected using
the Noraxon MyoSystem 1200 (Noraxon, Arizona, USA) 4-channel EMG system to collect data
on a computer program that was processed and analyzed. The lower trapezius EMG activity is
collected during therapeutic exercise and the skin is prepared prior to electrode placement by
shaving the hair (if necessary), scraping the skin with fine sandpaper, and cleansing the skin with
isopropyl alcohol to reduce skin impedance.
Figure 4: Placement of surface electrodes for the lower trapezius muscle.
Data collection for each subject begins by first recording the resting level of EMG electrical
activity. Post-workout EMG data is fixed and smoothed in the root mean square

81
within a 150ms window and MVIC is normalized through a 500ms window. ECG reduction is
also used if ECG rhythm is present in the data.
During the protocol, EMG data was recorded during a series of three isometric
contractions selected to obtain the maximum voluntary isometric contraction (MVIC) of the lower
trapezius muscle that was tested and maintained for three seconds in a position specific to the
desired muscle (Kendall, 2005) (Figure 5). The MVIC test consists of manual resistance
administered by the investigator, physical therapist, and metronome used to control the duration
of contractions.
Figure 5: MVIC position for the trapezius under the chin, shoulders in 125° abduction and the
MVIC action will be held at arm elevation.
All analyses were performed using the statistical software SPSS (SPSS Science Inc,
Chicago, Illinois) with significance set at a level of p ≤ 0.05. A 3x7 iterative measurement variance
analysis (ANOVA) was used to test the hypothesis. The Mauchly roundness test is significant in
phase one and phase two, therefore the Huynh-Feldt correction for both phases. Tukey's post-hoc
test is used in phase one and phase two and the adjustment of the least significant differences for
some comparisons is used in the average comparison.
3.3 RESULT
Our data revealed no significant difference in the activation of lower trapezius EMG with
varying posture in phase one participants. Pairwise comparison between Group 1 and Group 2 (p

SF SF
82
= 0.371) p Group 2 and Group 3 (p = 0.635, and Group 1 and Group 3 (p = 0.176 (Table 12).
However, statistical differences do exist between exercises. All exercises are

83
Table 12: Comparison of pairs of 3 groups in phase 1
Parable
Meaning
Group 1
v
Group 2
.371
Group 3
.176
Group 2
v
Group 3
.635
statistically significant from the others with the exception of exercises 1 and 6 for lower trapezius
activation (p = .323), exercises 3 and 5 (p = .783), and exercises 4 and 7 (p = .398). In addition,
some exercises showed the highest EMG activity of the lower trapezius including exercises 2, 6,
and 1. Exercise 2 showed 73.9% (Group 1), 88.9% (Group 2), and 73.6% (Group 3)
%MVIC activates the EMG of the lower trapezius. Exercise 6 showed 58.5% (Group 1), 79.2%
(Group 2), and 47.9% (Group 3) %MVIC EMG lower trapezius activation. Finally, exercise 1
showed 59.7% (Group 1), 59.5% (Group 2), and 57.4% (Group 3) %MVIC EMG activation of the
lower trapezius. Overall exercise 2 shows the largest EMG activation of the lower trapezius.
Our data showed no significant difference in lower trapezius EMG activation with varying
posture when comparing Group 1 to Group 2 (p=.161) and when comparing Group 3 to Group 1
(p=.304) in phase two participants (Table 13). However, a significant difference was obtained
when comparing Group 2 with Group 3 (p=0.021). In general, Group 3 showed higher
Table 13: Comparison of pairs of 3 groups in phase 2
Parable
Meaning
Group 1
v
Group 2
.161
Group 3
.304
84
Group 2
v
Group 3
.021
Lower trapezius EMG activity in each exercise when compared to Group 2. Also, there are
statistical differences between exercises. All exercises were statistically significant from the others
for lower trapezius activation with the exception of exercises 2 and 6 (p = 0.481), exercises 3 and
4 (p = 0.270), exercises 3 and 5 (p = 0.408), and exercises 3 and 7 (p = 0.531). Also, some

85
exercises showed the highest %MVIC EMG activity of the lower trapezius including exercises 2,
6, and 1. Exercise 2 showed an average of 76.4% (Group 1), 55.3% (Group 2), and 80.1% (Group
3) %MVIC EMG activation of the lower trapezius. Exercise 6 showed 80.3% (Group 1), 43.9%
(Group 2), and 73% (Group 3) activation of the MVIC EMG of the lower trapezius. Last
exercise 1 showed 48.9% (Group 1), 39.3% (Group 2), and 60.8% (Group 3) %MVIC EMG lower
trapezius activation. Overall exercise 2 showed the largest EMG activation of the lower trapezius
and Group 3 showed the highest percentage of 80.1% (Table 14).
Table 14: Percentage of MVICs
indicated by exercise 2 across all
Group
Group 1
76.4%
Group 2
55.27%
Group 3
80.1%
3.4 DISCUSSION
Our data showed no difference between EMG activation in different postures in phase one and
phase two except for Groups 2 and 3 in phase two, which is contrary to what other authors have
shown (Reinold, et al., 2004; De Mey, et. al., 2013). However, in phase 2, Group 2 (Leg staggered
group) performed standing resistance band exercises and Group 3 (Conscious correction group)
performed lying on a mat while the physical therapist motioned the participants to contract the
lower trapezius during repetitions. This provides some evidence of the need for individuals, who
have shoulder bumps, to have a supervised rehabilitation program. Although there was no
statistical difference between Groups one and three in phase 2, each exercise in Group 3 showed

86
higher EMG activation than a lower trapezius than Groups 1 and 2 except for exercise 6 in Group
1 (Group 1 = 80%, Group 3 = 73%). Although the data is not statistically significant, it is important
to note that the project looked at many exercises which made it more difficult to show significant
differences between the Groups. This is possible

87
warrant further research looking at the exercise of individuals with altered posture and their effects
on EMG activation.
When looking at the exercises that showed the highest EMG activation, phase one 2 exercises
showed the highest EMG activation in 73.9% (Group 1), 88.9% (Group 2), and 73.6% (Group 3)
participants and there was no statistical difference between the groups. Phase
2 participants also showed high EMG activation in the lower trapezius in exercise two 76.4%
(Group 1), 55.3% (Group 2), and 80.1% (Group 3). Overall this exercise showed the highest EMG
activity of the lower trapezius which showed the importance of activating the lower trap during
therapeutic exercise in rehabilitation patients. Previous studies have shown horizontal abduction of
the stomach at 135° with external rotation (97±16% MVIC; Ekstrom, Donatelli, & Soderberg, 2003)
to show high EMG activity of the lower trapezius.
Therefore, in both phases of horizontal abduction on the stomach at 130° with external rotation
exercises is the optimal exercise to activate the lower trapezius.
Exercise 6 also showed high EMG activity of the lower trapezius in both phases. In phase one,
exercise 6 showed 58.5% (Group 1), 79.2% (Group 2), and .47.9% (Group 3) %MVIC EMG
activation of lower trapezius and in phase two exercise 6 showed 80.3% (Group 1), 43.9% (Group
2), and 73% (Group 3) %MVIC EMG activation of lower trapezius activation. Previous research
has shown external rotation standing at 90° abduction (88±51% MVIC; Myers, Pasquale, Laudner,
Sell, Bradle, & Lephart, 2005) had high EMG activation of the lower trapezius, which was
comparable to Group 2 postures in phases one (79.2%) and two (43.9%). Both groups appear to
be consistent in previous research findings on lower trapezius activation.

88
Previous research has also shown a vulnerable external rotation at 90° abduction (79±21%
MVIC; Ekstrom, Donatelli, & Soderberg, 2003) show high EMG activation of the lower trapezius.
This compares to exercise 6 in Group 1 (58.5%) and Group 3 (0.47.9%) in phase one and Group
1 (80.3%) and Group 3 in phase 2 (73%). Our results appear to be comparable to previous research
on EMG activation from this exercise. Exercise 1 also showed the activation of high-medium
lower trapezius, which was comparable to previous studies. In phase one, exercise 1 showed 59.7%
(Group 1), 59.5% (Group 2), and 57.4% (Group 3) and in phase two exercise 1
showed 48.9% (Group 1), 39.3% (Group 2), and 60.8% (Group 3) EMG activation from the lower
trapezius. Previous studies have shown horizontal abduction is prone to 90° abduction with
external rotation (74±21% MVIC; Ekstrom, Donatelli, & Soderberg, 2003)(63±41%MVIC;
Moseley, Jobe, Pink, Perry, & Tibone, 1992) showed moderate to high EMG activation, which
was comparable to Phase One Group 1 (59.7%), Phase One Group 3 (57.4%), Phase Two Group
1 (48.9%), and Phase Two Group 3 (60.8%). Our results appear to be comparable to previous
studies.
An inherent limitation exists using surface EMG (sEMG) because the attachment point is the
skin moving, and the mobility of the skin makes it difficult to test the same area in different
exercises. Another limitation is the possibility that some electrical activity comes from another
muscle that has not been studied, called crosstalk (Solomonow, et al., 1994). In this study, subjects
also had varying amounts of subcutaneous fat, which may have affected crosstalk in the amplitude
of sEMG (Solomonow, et al., 1994; Jaggi, et al., 2009). Other limitations include the fact that
phase two participants are currently undergoing physical therapy and may have done some
exercises in a rehabilitation program, which would increase their familiarity with the exercises
compared to phase one participants.

89
In the determination of weight selection, a standardized formula is used, which calculates the
weight of individuals, based on their anthropometry. This limits the number of interpretations
because individuals do not all perform at the same level of their maximum rep %, which can
reduce or increase individual strain levels and alter the interpretation of EMG. One reason for the
lack of statistically significant differences may be that participants did not perform the maximum
repetition test and determine the weight to be used from the percentage of one max repetition.
This may have resulted in higher EMG activation in certain Groups or individuals. In addition,
strenuous exertion may have caused sweating or changes in skin temperature that may have
decreased the adhesion of electrodes and/or skin markers, where by altering EMG signals.
Intra-individual errors between movements and between groups (healthy vs. pathological)
and intra-observer variance can also add variance to the results. Although individuals in phase 2
are screened for pain during the project, pain in pathological populations may not allow
individuals to perform specific movements, which is a limitation specific to this population.
3.5 CONCLUSION
In conclusion, 130 vulnerable abductions with external rotation training showed a
maximum %MVIC activation profile for the lower trapezius. Unfortunately, no differences were
shown in the Group to correlate changes in posture with increased EMG activation in the lower
trapezius; However, this may require further research examining each exercise individually.
3.6 CONFESSION
I would like to thank Dennis Landin for his helpful guidance on this project, Phil Page for giving
me the tools to perform EMG analysis, and Peak Performance Physical Therapy
to provide facilities for this project.

90
CHAPTER 4: EFFECT OF LOWER TRAPEZIUS FATIGUE ON SCAPULAR
DISCINESIS IN INDIVIDUALS WITH HEALTHY PAIN-FREE SHOULDER
COMPLEXES
4.1 INTRODUCTION
Subacromial impingement is used to describe the decrease in the distance between the
inferior boundary of the acromion and the superior boundary of the humerus head and the
proposed precursor includes altered scapula kinematics or scapula discinesis. The proposed study
examined the effects of lower trapezius fatigue on scapula discinesis in a healthy adult male
population with a pain-free shoulder complex (dominant arm). During the study, subjects were
under the supervision and guidance of a licensed physical therapist while each individual
performed a fatigue protocol on the lower trapezius, a passive stretching protocol on the lower
trapezius, and individuals were evaluated for scapular dyskinesis and muscle weakness before and
after the protocol.
Subacromial impingement is determined by a decrease in the distance between the inferior
boundary of the acromion and the superior boundary of the head of the humerus (Neer, 1972). It
has been shown to cause compression and potential damage to soft tissues including: supraspinatus
tendon, subacromial bursa, long head biceps tendon, and shoulder capsule (Bey, et al., 2007;
Flatow, et al., 1994; McFarland, et al., 1999; Michener, et al., 2003). These impacts, often a
precursor to rotator cuff tears, have been shown to result from (1) translations of superior humerus
heads (2) altered scapula kinematics (Grieve & Dickerson, 2008), or a combination of both. The
first mechanism, superior humerus translation, has been associated with rotator cuff fatigue,
(Chen, et al., 1999; Chopp, et al., 2010; Cote, et al., 2009; Teyhen, et al., 2008) and confirmation
has been achieved radiographically following a common cuff rotator fatigue protocol (Chopp, et

91
al., 2010). The second previously proposed mechanism for impact has been
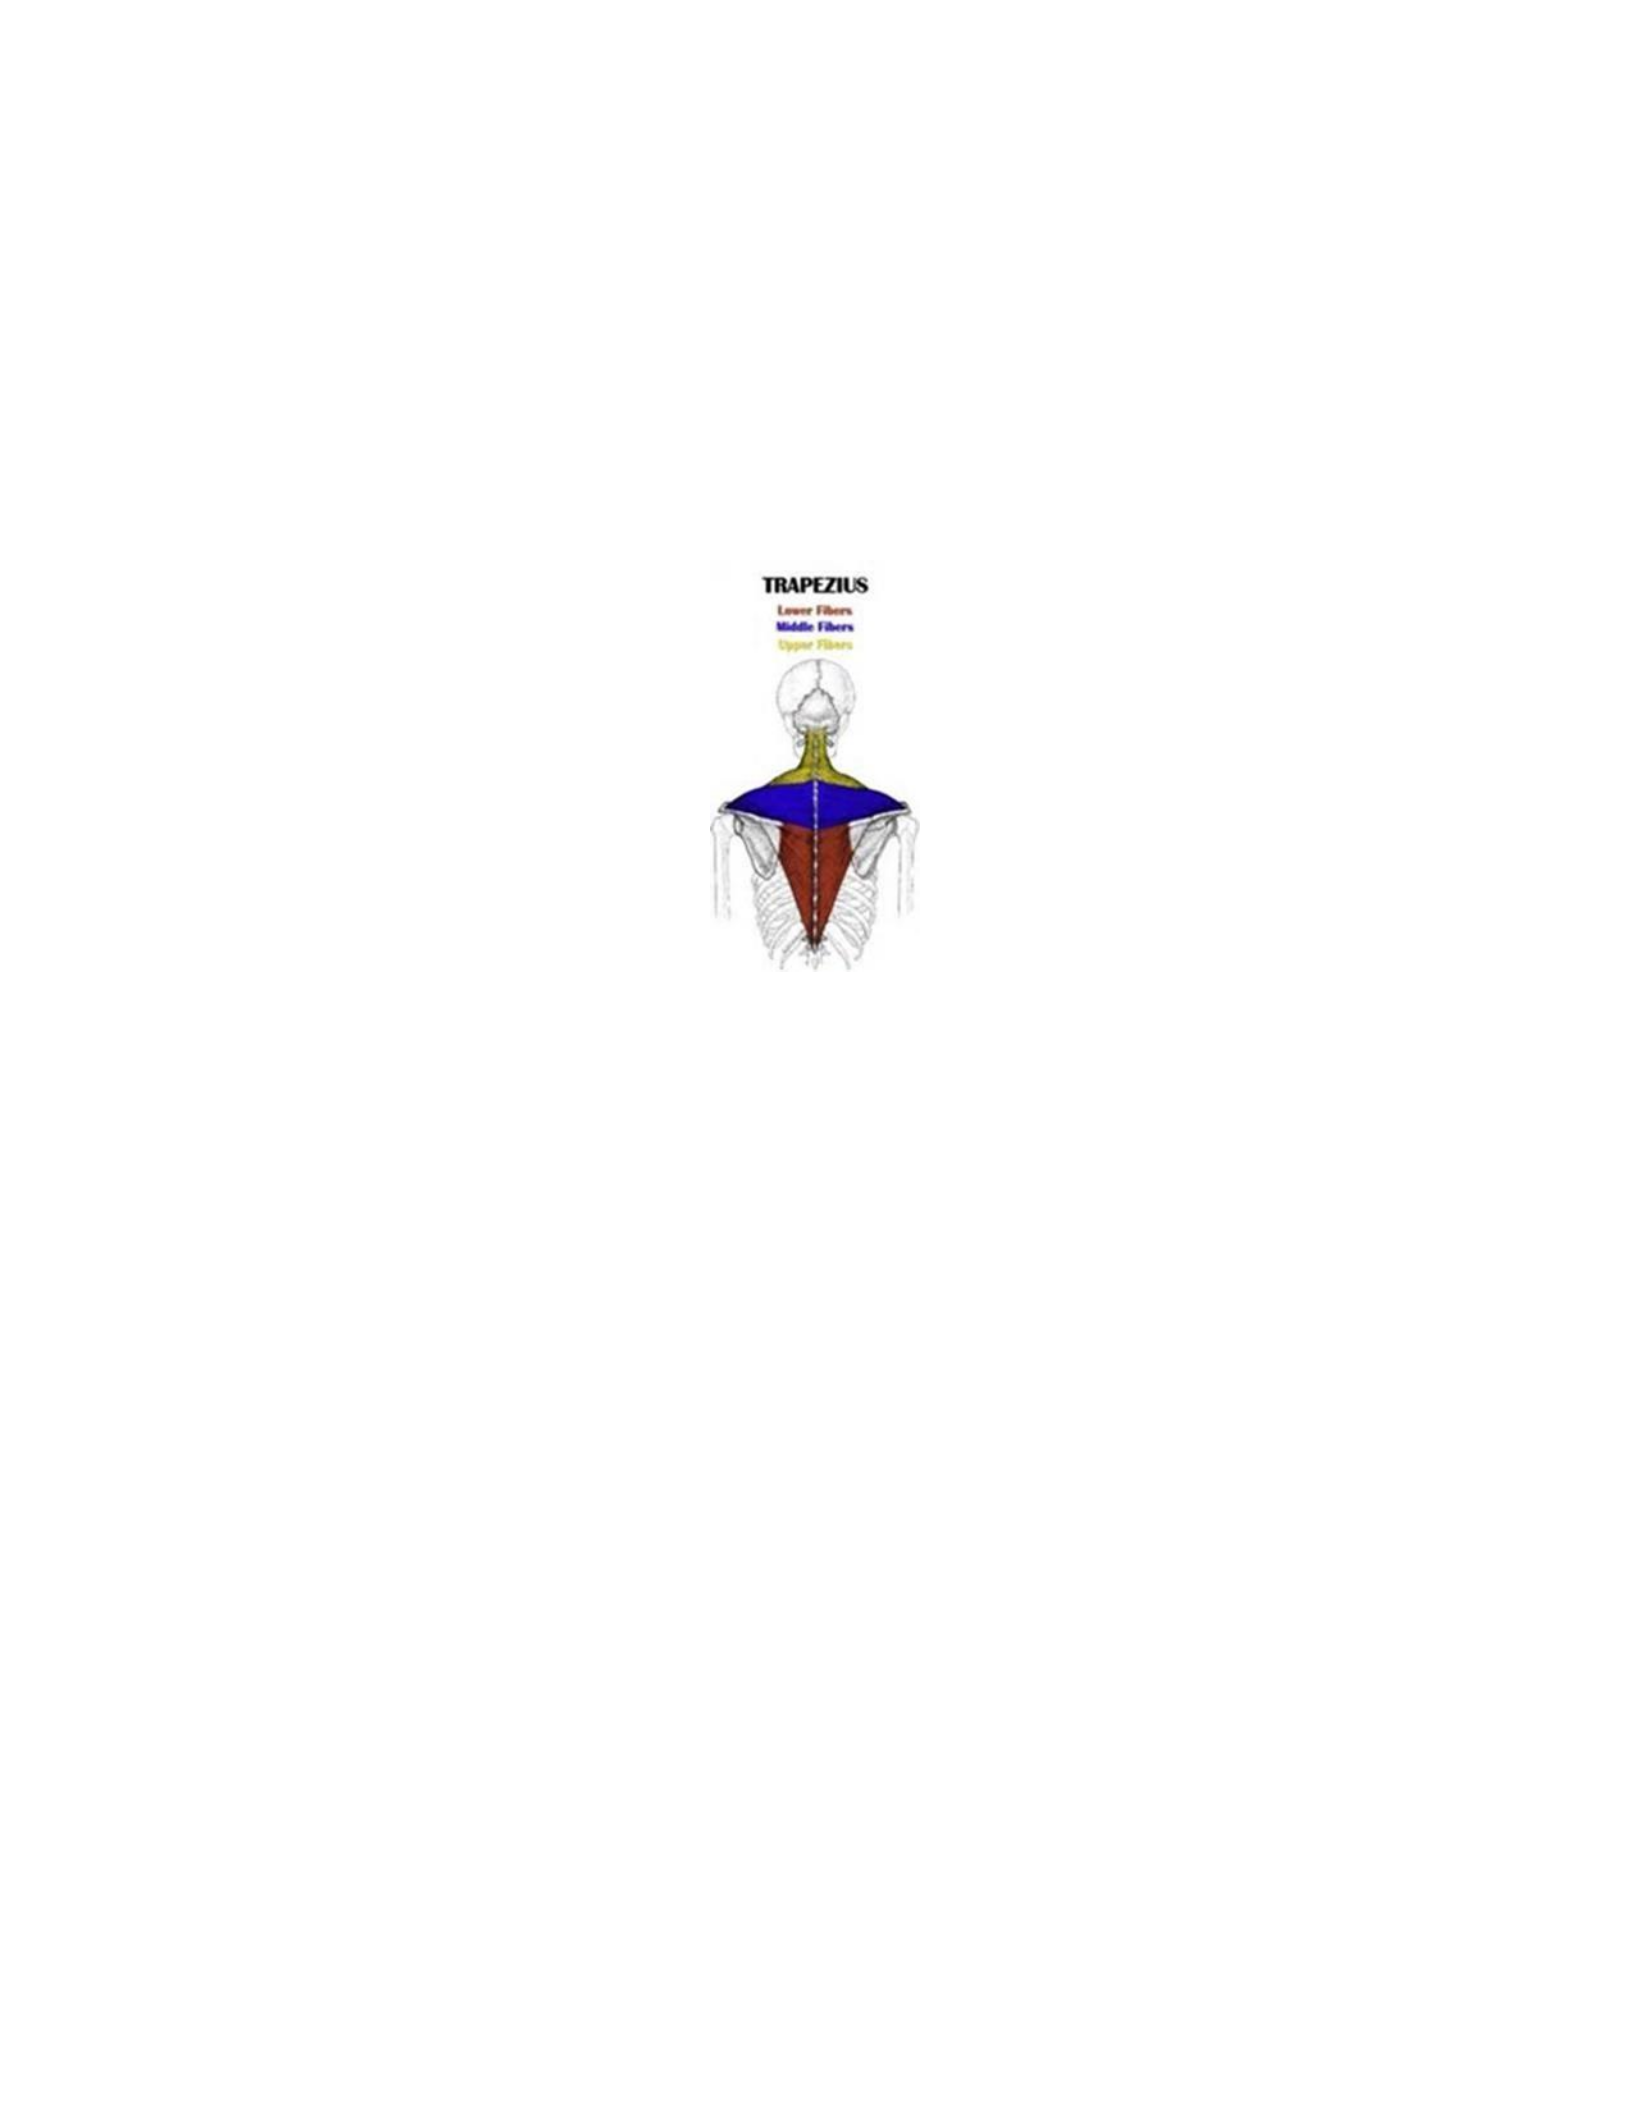
92
has altered scaular kinematics during movement. Individuals diagnosed with shoulder
impingement have shown muscle imbalances in the shoulder complex and in particular in the force
pairs responsible for controlled scapular movement. The lower trapezius, upper trapezius and
anterior serratus have been included as target muscles in this style pair (Figure 6).
Figure 6: Trapetic muscles
During asymptomatic arm elevation in the shoulder, upward rotation, posterior tilt, and
scapula retraction have been shown (Michener, et al., 2003). However, for individuals diagnosed
with subachromial impingement or shoulder dysfunction, these movements have been impaired
(Endo, et al., 2001; Lin, et al., 2005; Ludewig & Cook, 2000). Endo et al. (2001) examined scapular
orientation through radiographic assessment in patients with shoulder impact and healthy controls,
taking radiographs at three abduction angles: 0°, 45°, and 90°. Patients with unilateral stretch
syndrome experienced a significant decrease in upward rotation and posterior tilt of the scapula
compared to the contralateral arm, and this decrease was more pronounced when the arm was
abducted from neutral (0°). This decrease is absent in both healthy control shoulders; Thus the
change seems to be related to impact.

93
Previous research has shown that external rotator muscle fatigue of the shoulder
contributes to changes in scapular muscle activation and kinematics (Joshi, et al., 2011), but to the
knowledge of this author, no previous article has examined the fatigue effects of the lower
trapezius The lower trapezius and anterior serratus have been generally accepted as scapular
stabilizing muscles, which have resulted in upward rotation of the scapula, posterior tilt, and
retraction during arm elevation. It has been anticipated that by functionally weakening these
muscles through fatigue, a change in scapular orientation similar to an impact should occur. In the
previous external rotator fatigue protocol of the shoulder from pre-fatigue to post-fatigue, the
activation of the lower trapezius decreased by 4% and the upward rotational movement of the
scapular increased in the ascending phase by 3° while the activation of the serratus remained
unchanged from pre-fatigue to post-fatigue (Joshi, et al., 2011). The authors concluded that
changes in the lower trapezius due to fatigue of the shoulder's external rotator muscles can lead to
shoulder injury and have contributed to changes in scapula movement.
Scapula dysfunction or scapula discinesis has been defined as abnormal movement or
position of the scapula during movement (McClure, et al., 2009). This altered kinematics is caused
by shoulder injuries such as impingements or by changes in muscle strength pairs (Forthomme,
Crielaard & Croisier, 2008; Kolber & Corrao, 2011; Cools, et al., 2007). Kibler et al. (2002)
published a classification system for scapular discinesis for use during clinical practical visual
observation. This classification system has included three abnormal patterns and one normal
pattern of scapula movement. Type I patterns, characterized by inferior angular protrusions, have
been present when an increase in the protrusion or inferior angular protrusion (increased anterior
slope) of the scapula is noted along the horizontal axis parallel to the scapula spine. Type II
patterns, characterized by medial border protrusions, are present

94
When the entire medial boundary of the scapula is more prominent or prominent (increased
internal rotation of the scapula) which represents excessive movement along the vertical axis
parallel to the spine. The type III pattern, which is characterized by a superior scapula bulge, has
been present when excessive upward movement (elevation) of the scapula is present along the
axis in the sagittal plane. The type IV pattern is considered a normal scapulohumeral movement
without excess protrusion of the scapula and symmetrical movement to the contralateral
extremities (Kibler, et al., 2002).
According to Burkhart et al., scaular dysfunction has been shown in asymptomatic
overhead athletes (Burkhart, Morgan, & Kibler, 2003). Therefore, dyskinesis can also be a factor
causing a variety of shoulder injuries not only as a result. Importantly, the lower trapezius has
formed and contributes to the pairing of strength with other shoulder muscles and the general
consensus of current research has been that the weakness of the lower trapezius has been a
predisposing factor for shoulder injuries although little data suggests this theory (Joshi, et al.,
2011; Cool, et. al., 2007) However, one study has shown that scapula dyskinesis can occur in the
asymptomatic shoulder of a competitive swimmer during a training session (Madsen, Bak, Jensen,
& Welter, 2011). Previous authors (Madsen, et al., 2011) have shown that training fatigue can
induce scapula dyskinesis in healthy adults without shoulder problems and current research has
stated that lower trapezius can affect and individuals to scapula injury and dyskinesis. However,
limited data has bolstered this latter claim, and current research lacks information on what
qualifies as a weakness or strength.
Therefore, the purpose of this study is to look at asymptomatic shoulders for lower trapezius
weakness using a handheld dynamometer and scapula discinement due to fatigue and stretching
protocols.

95
Therefore, our goal is to determine whether strength, endurance, or stretching of the lower
trapezius will have an effect on inducing scapula discinesis. The purpose of this study was to
identify whether fatigue or stretching can cause scapula discinesis in healthy adults and make
individuals susceptible to shoulder impingements. We base the laborious protocol on previous
studies that have been shown to produce known changes in the orientation of the scapula (Chopp,
et al., 2010; Tsai, et al., 2003) and in previous studies and studies that have shown exercises with
high EMG activity profiles of lower trapezius (Coulon & Landin, 2014). Previous studies have
consistently shown that acute stretching attacks reduce force-generating capacity (Behm, et al.,
2001; Fowles, et al., 2000; Kokkonen, et al., 1998; Nelson, et al., 2001), which led us in the current
investigation to hypothesize that the reduction would translate into increased muscle fatigue.
The study has helped answer two questions that are currently open. First, we have shown
that lower trapezius fatigue can induce scapula dyskinesis in healthy individuals as classified by
the Kibler classification system. Second, we have provided more clarity on which mechanism
(superior humerus translation or altered scapular kinematics) predominates the changes in the
subachromial space after fatigue. Finally, we have determined whether there is a difference in
fatigue levels after a stretching protocol or an endurance training protocol and if one of them
causes scapulae discinesis.
4.2 METHOD
The proposed study examined the effects of lower trapezius fatigue on scapular dyskinesis
in 15 healthy men with pain-free shoulder complexes (dominant arms). During the study, subjects
were under the supervision and guidance of a licensed physical therapist with each individual
performing a fatigue protocol on the lower trapezius, a passive stretching protocol on the lower
trapezius, and an individual evaluation for scapular dyskinesis and muscle weakness

96
before and after protocols. The exercise consisted of exercises (horizontal abduction of the
stomach
97
at 130° abduction) was specifically selected because it showed high EMG activity in the lower
trapezius of previous work (Coulon & Landin, 2012) and research (Ekstrom, Donatelli, &
Soderberg, 2003) (Figure 7).
LEARN
EMG Activation (%MVIC)
Coulon & Landin, 2012
80.1%
Ekstrom, Donatelli, & Soderberg,
2003
97%
Figure 7: Activation of the lower trapezius EMG during horizontal abduction on the stomach at
130° abduction
The stretching protocol consists of passive stretching that attempts to increase the distance
from the origin (spinosus process of the T7-T12 vertebrae) to the insertion (spinal scapula) as
described earlier (Moore & Dalley, 2006). There is a minimum of ten days between protocols if
the fatigue protocol is done first and three days between protocols if the stretching protocol is
done first. The extended amount of time given to the fatigue protocol due to delayed-onset muscle
pain has been shown to cause adverse effects of complex shoulder movement and strength
production and previous studies have shown these effects have been cured within ten days (Braun
& Dutto, 2003; Szymanski, 2001; Pettitt, et al., 2010).
After obtaining approval, subjects were familiarized with the perceived exertion scale
(PES) and assessed their pretest fatigue levels. Subjects were instructed to warm up for 5 minutes
at resistance level one on the upper body ergometer (UBE). After the subjects completed heating,
the isometric strength of the lower trapezius was assessed using a handheld dynamometer
(microFET2, Hoggan Scientific LLC, Salt Lake City, UT). The isometric grip was rated 3 times
and the average of the 3 trials was used as the pre-fatigue strength score. The isometric holding

98
position used for the lower trapezius has been described in previous studies (Kendall, et al.,

99
2005)(Figure 8) and a handheld dynamometer is attached to a platform device, which the subject
is pushed at a specific point of contact.
Figure 8: The MMT position for the lower trapezius will be prone to the stomach, shoulder in a
125-130° abduction and the action will be rejected arm elevation relative to the device (not
shown).
The 22-inch lever arm measurement is taken from the acromion to the wrist for each
individual and is the point of contact for isometric testing. After dynamometric testing, a visual
observation classification system was used to classify the subject's scapular discinestic pattern
(Kibler, et al., 2002). The subject was then given instructions on how to perform a horizontal
abduction on the stomach at the 130° exercise. In this exercise, the subject is positioned on his
stomach with his shoulders resting on flexion 90° forward. From this position, the subject abducts
the arm horizontally while maintaining the shoulder at a 130° abduction (as measured by a
licensed physical therapist with a goniometric device) with the shoulder in an external rotation
(thumb up) until the arm reaches the frontal plane (Figure 9).
Figure 9: Horizontal abduction prone at 130° abduction (goniometric device not depicted)

100
This exercise is designed to isolate the lower trapezius muscles and is therefore used to
facilitate lower trapezius fatigue. Percentage of these MVIC and EMG profiles

101
Training is 97% for the lower trapezius, 101% for the middle trapezius, 78% for the upper
trapezius, and 43% for the anterior serratius (Ekstrom, Donatelli, & Soderberg, 2003). Data
collection for each subject begins with a series of three isometric contractions that are averaged
and a system of classification of scapula and lateral scapula glide tests allows for scapula
assessment and is performed before and after each fatigue protocol.
Once the subjects were comfortable with the lower trapezius exercise, they were then
instructed to complete this exercise for two minutes at a rate of 30 repetitions per minute
(metronome assisted) using dumbbell weights and maintaining scapular pressure. Each subject
performs the repetition of each exercise at a regulated repetition rate with the use of a metronome
set to 60 beats per minute. The subject performs each concentric and eccentric phase of the exercise
for two taps. The repetition rate was set by the metronome and all subjects used a weighted
resistance of 15%-20% of their average maximum isometric containment assessment. Subjects
were asked to assess their level of fatigue using PES after 2 minutes (Figure 10) and given
maximum boost during exercise.
Figure 10: Perceived Exertion Scale (PES) (Adapted from Borg, 1998)
102
The subjects were then given a one-minute break before doing the exercise for another
two minutes. This process was repeated until they could no longer do the exercises and reported
20 to the PES. This strenuous activity is unilateral in nature and once fatigue is achieved, the
isometric strength of the trapezius under the subject is assessed again using a handheld
dynamometer. The isometric grip was rated three times and the average of the three trials was
used as post-fatigue strength. Then the scapula classification system and lateral scapula slide test
were reassessed.
Participants in this study must meet the inclusion/exclusion criteria. The inclusion criteria
for all subjects are: 1) age 18-65 years, and 2) able to communicate in English. Exclusion criteria
from the Healthy adult group include: 1) a recent history (less than 1 year) of musculoskeletal
injury, condition, or surgery involving the upper extremities or cervical spine, and 2) a previous
history of neuromuscular conditions, pathologies, or numbness or tingling in both upper
extremities. Subjects are also excluded if they show contraindications to exercise (Table 15).
Table 15: Contraindications to exercise
1.
recent changes in resting ECG indicating significant
ischemia
2.
recent myocardial infarction (within 7 days),
3.
Acute cardiac events
4.
Unstable angina
5.
Uncontrolled cardiac dysrhythmia
6.
stenosis aorta parah simtomatik
7.
uncontrolled symptomatic heart failure
8.
acute pulmonary embolism or pulmonary infarction

103
9.
acute myocarditis or pericarditis
10.
suspected or known to have aneurysm surgery
11.
Acute systemic infection is accompanied by fever,
body pain, or swollen lymph nodes.
Participants were recruited from Louisiana State University students, pre-physical therapy
students, and healthy individuals willing to volunteer. Participants fill out informed consent, PAR-
Q, HIPAA authorization agreement, and meet inclusion and exclusion criteria

104
through the use of verbal questionnaires. Each participant was blinded to the expected results and
hypothesized research results. The data were processed and this study will look at differences in
muscle strength production, scapula slide tests, and scapula discinesis classification.
Fifteen men participated in the study and data were collected from their dominant upper
extremities (13 right extremities and 2 left upper extremities). The sample size was determined by
power analysis using the results of previous studies (Chopp, et al., 2011; Noguchi, et al., 2013);
Fifteen participants are required for adequate power. Height, weight, and average age are
69.27 inches (range 66 to 75), weigh 175.8 pounds (range 150 to 215), and age 24.67 years (range
20 to 57 years). Participants were excluded from the study if they reported pain or injury to the
upper extremities within the past year, or structural damage to the bones (head humerus, clavicle
or acromion fractures, or joint dislocations). The study was approved by the Louisiana State
University Institutional Review Board, and each participant gave informed consent.
The researchers conducted assessments for inclusion and exclusion criteria through the
use of verbal questionnaires and PAR-Q. The study is explained to all subjects and they read and
sign the consent agreement approved by the university's institutional review board. On the first
day of testing, subjects were informed of their rights and procedures to participate in the study,
discuss and sign informed consents, read and sign HIPPA authorizations, discuss inclusion and
exclusion criteria, receive a brief screening check, and be oriented to the testing protocol.
The fatigue protocols are sorted as follows: pre-fatigue testing, practice and habituation,
two-minute fatigue and one-minute rest (repetitive) protocols, post-fatigue testing. The stretching
protocols are sorted as follows: pre-stretching testing, practice and

105
Familiarization, manual stretching protocols (three stretches for 65 seconds each), one-minute
breaks (after each stretch), and post-stretch testing. In total, individuals are tested over two testing
periods, with a minimum of ten days between protocols if the fatigue protocol is performed first
and three days between protocols if the stretching protocol is performed first. An extended amount
of time is given to the fatigue protocol because delayed-onset muscle pain can cause adverse
effects of complex shoulder movement and strength production and previous studies have shown
these effects have resolved within ten days (Braun & Dutto, 2003; Szymanski, 2001).
The fatigue protocol consists of five parts: (1) kinematic evaluation of the pre-fatigue
scapula, (2) muscle-specific maximum voluntary contraction, which is used to determine max
repetition and weight selection, (3) load scaling used during the fatigue protocol, (4) horizontal
abduction of the prone at 130° fatigue task, and (5) kinematic evaluation of the post-fatigue
scapula.
The stretching protocol consists of four parts: (1) pre-stretch scapula kinematic evaluation, (2)
muscle-specific maximum voluntary contraction, (3) manual lower trapezius stretching
performed by a physical therapist performed on the stomach, and (5) post-stretch scapula
kinematic evaluation.
Participants performed three repetitions of the lower trapezius muscle-specific maximal
voluntary contraction (MVC) against a stationary device using a handheld dynamometer
(microFET2, Hoggan Scientific LLC, Salt Lake City, UT). A two-minute rest period is provided
between each activity to reduce the likelihood of fatigue (Knutson, et al., 1994; Chopp, et al.,
2010) and MVC have been formed before and after stretching and fatigue protocols. During the
grueling protocol, participants hold the weight in their hands (determined between 15%-20% of
the MVC) with their thumbs facing up and grasp tightly on the dumbbell.

106
The pre-fatigue trial consisted of obtaining the MVC test level during isometric grip and
evaluation/scapular orientation measurements at various angles of humerus elevation and during
active elevation. The data were then compared with the post-fatigue trial. To avoid residual fatigue
from MVC, participants were given a break of about five minutes before pre-fatigue
measurements.
The grueling protocol consisted of repeated voluntary movements from horizontal
abduction on the stomach at 130° that were repeated until exhaustion. The task consists of
repeatedly lifting dumbbells with the thumb up and a firm grip on dumbbell loads from 90°
shoulder flexion with 0° elbow flexion to 180° shoulder flexion with 0° elbow flexion at a
controlled speed of 60 bpm (controlled by the metronome) until tired. The subject performs each
task for two minutes and the subject is given a one-minute break before performing the task for
another two minutes. The subject repeats the process until the task can no longer be performed
and the subject reports 20 on the PES. The subjects performed fatigue activities unilaterally and
once fatigue was achieved, the isometric strength of the subject's lower trapezius was assessed
using a handheld dynamometer. The isometric grip was rated three times and the average of the
three trials was used as post-fatigue strength. Subjects are also classified by a scapular discinestic
classification system and the data are analyzed. All arm angles during the task were positioned by
the experiment using a manual goniometer.
During the protocol, verbal coaching and maximum encouragement are continuously
provided by the researcher to promote scapula retraction and subsequent scapula stabilizer fatigue.
Fatigue was monitored using the Borg Perceived Exertion Scale (PES) (Borg, 1982). The
participants verbally expressed PES before and after every two minutes of the fatigue test during
the fatigue protocol. Participants continue the protocol until the "failure" as determined by the
previous

107
Research on scapula retractor fatigue (Tyler, et al., 2009; Noguchi, et al., 2013). Subjects are
considered failed when the subject verbally shows fatigue (PES 20), the subject shows and an
inability to maintain repetitions at 60 bpm, subjects exhibit an inability to fully retract the scapula
before exercising on three consecutive repetitions, and subjects exhibit an inability to break the
frontal plane in the cranial region with the elbow on three consecutive repetitions.
Fifteen healthy adult men without shoulder pathology in their dominant shoulder
performed a stretching protocol. After obtaining consent, subjects were familiarized with the
perceived exertion scale (PES) and asked to assess their pretest fatigue levels. Subjects were
instructed to warm up for five minutes at resistance level one on an upper body ergometer (UBE).
After the heating was complete, the examiner assessed the isometric strength of the bottom
trapezius using a handheld dynamometer (microFET2, Hoggan Scientific LLC, Salt Lake City,
UT). The isometric grip was rated three times and the average of the three trials showed a pre-
fatigue strength score. The isometric holding position used for the lower trapezius was described
in previous studies (Kendall et al, 2005); The handheld dynamometer is attached to the platform
and the subject is then pushed into the device. Prior to dynamometry testing, visual observation
classification systems classified subject's scapular discinestic patterns (Kibler, et al., 2002). The
subject was then manually stretched which attempted to increase the distance from the origin (the
T7-T12 thoracic vertebral spinosus process) to the insertion (scapula spine) as described earlier
(Moore & Dalley, 2006). The examiner performed three passive stretches and held each for 65
seconds because only long-duration stretches (>60 seconds) performed in a pre-workout routine
have been shown to compromise maximal muscle performance and are hypothesized to induce
scapula discinesis. The examiner performs stretching activities

108
Unilaterally and after being performed, the isometric strength of the trapezius under the subject
was assessed using a handheld dynamometer. The isometric grip was rated 3 times and the
average of the 3 experiments was then used as post-stretch strength. Finally, the subjects are
classified into a scapular discinesis classification system and all data will be analyzed.
Post-fatigue trials were collected using protocols identical to those described in the pre-
fatigue trials. To prevent fatigue recovery from messing with the data, the examiner provides a
post-fatigue trial immediately after completing the fatigue or stretching protocol.
When evaluating the scapula, the examiner observes the resting and dynamic position and
movement patterns of the scapula to determine if there is a deviation in position or movement
(Magee, 2008; Ludewig & Reynolds, 2009; Wright, et al., 2012). This classification system
(discussed earlier in this paper) consists of three abnormal patterns and one normal pattern of
scapula movement. (Kibler, et al., 2002). Testers used two observational methods. First, determine
whether the individual exhibits scapula discinesis by the YES/NO method and secondarily
determine what type the individual exhibits (type I-type IV). Sensitivity (76%), inter-appraiser
agreement (79%), and positive prediction values (74%) have all been documented (Kibler, et al.,
2002). The second method used is the lateral scapula shear test, a semi-dynamic test used to
evaluate the position of the scapula and the strength of the scapula stabilizer. The test was
performed in three positions (arm at the side, hand at hip, 90° glenohumeral abduction with full
internal rotation) measured (cm) from the inferior angle of the scapula to the spinosus process in
a direct horizontal line. A positive test consists of a difference greater than 1,5 cm between the
sides and shows a deficit in dynamic stabilization or postural adaptation. The reliability of the ICC
(.84) and inter-tester (.88) has been determined for this test (Kibler, 1998).

109
The paired sample t-test is used to determine the difference in lower trapezius muscle
testing and stretching between pre-fatigue and post-fatigue conditions. All analyses were
conducted using the Statistical Package for Social Sciences version 12.0 (SPSS, Inc, Chicago, IL)
software. The probability alpha level of 0.05 is set a priori to be considered statistically significant.
4.3 RESULT
The data showed a statistically significant difference between the fatigue and stretching
groups (p = 0.002). The stretching group did not show the pre-stretching protocol of scapula
discinesis and the post-stretching protocol in the scapula classification system or the 3-phase
scapula shear test (arm at the side, hand at the hip, 90° glenohumeral abduction with full internal
rotation of the humerus). However, a statistically significant difference (p<.001) was observed in
the pre-stretch MVC test (25.1556 pounds) and the post-stretch MVC test (24.5556 pounds). This
is a 2,385% decrease in force production after stretching.
In the pre-testing of the pre-fatigue group, all participants did not show scapula discinesis
in the Yes/No classification system and all showed a pattern of type IV scapula movement before
the fatigue protocol. All participants were negative for the three phases of the scapula slide test
(arm at side, hand at hip, 90° glenohumeral abduction with full internal humerus rotation) with
the exception of one participant who had a positive result on 90° glenohumeral abduction with
full internal humerus rotation portion of the test. During the test, this participant reported that he
had participated in a fitness program before coming to his assessment.
Our data show a statistically significant difference (p<001) in pre-fatigue MVC (25.2444
pounds) and post-fatigue MVC (16.5333 pounds). This was a 34.5% decrease in power
production, and all participants showed an average MVC decrease with an average of 16.533
Pound. There is also a statistically significant difference in the production of the average force

110
before and

111
Post-fatigue exercise (p=<.001) that shows individuals showing true fatigue. In the post-fatigue
trial, all but four participants were classified as yes (73.3%) for scapula dyskinesis and the types
of post-fatigue dyskinesis were type I (6; 40%), type II (5; 33.33%), type III (0), and type IV (4;
26.67%). All participants were negative for the arm in the lateral phase of the scapula slide test
except participants 4,6,10,11,12, and 14 (6; 40%). All participants were negative for the hand
phase in the hip of the scapula slide test except participants 4, 6, 9, and 10 (4; 26.67%). All
participants were negative for 90° glenohumeral abduction with full humerus internal rotation
phase of the scapula shear test with the exception of participants 1, 2, 3, 4, 7, 8, 9, 10, 12, 13, and
14 (10; 66.67%).
The average number of grueling trials each participant completed was 8,466 with the
lowest being four trials and the longest being sixteen trials. The average weight used based on
MVC is 4.6 pounds with the lowest being four pounds and the highest being seven pounds.
4.4 DISCUSSION
In this study, the participants demonstrated scapula discinesis with exercises specifically
selected to fatigue the lower trapezius. The results are consistent with previous studies, which
have shown significant differences in upward rotation of the scapula and posterior slope for 0 to
45 degrees and 45 to 90 degrees of elevation (Chopp, Fischer, & Dickerson, 2010). The presence
of scapula discineosis provides some evidence that lower trapezius fatigue has a detrimental
effect on shoulder function and may lead to shoulder pathology. Also, these results show that the
proper function and training of the lower trapezius is essential for athletes above the head and
shoulder health.
By using a classification system, investigator bias is possible because
Participants and examiners participated in both sessions. Also, the physical examination test of the

ok
112
scapula has shown a moderate level of sensitivity and specificity (Table G in the Appendix) with

113
Previous research found sensitivity measurements from 28-96 depending on position
measurements and specificity ranging from 4-58.
The results of our study have also shown relevance for shoulder rehabilitation and injury
prevention programs. Fatigue induced through repeated overhead glenohumeral movements
while in external rotation results in changes in strength and endurance in the lower trapezius
muscle and scapular discinesis, and has been associated with numerous injuries, including
subacromial impacts, rotator cuff tears, and glenohumeral instability. Overcoming imbalances in
the lower trapezius through proper exercise is essential for establishing normal shoulder function
and health.
4.5 CONCLUSION
In conclusion, lower trapezius fatigue seems to contribute to or even lead to scapula
discinesia after a grueling task, which can identify precursors of injury in repetitive overhead
activities. This suggests the importance of overcoming lower trapezius endurance, especially in
overhead athletes, and the possibility that the lower trapezius is a key muscle in the rehabilitation
of scapula discinesis.

114
CHAPTER 5: SUMMARY AND CONCLUSION
In summary, shoulder impingement has been identified as a common problem in
populations with orthopedic disorders and scapula discineis is involved in this pathology. The
literature is uncertain about the causative factors of scapula dyskinesis in shoulder impingements
and no association has been shown regarding specific muscles contributing to biomechanical
abnormalities. These studies sought to demonstrate therapeutic exercises that specifically
activated the lower trapezius and used the appropriate exercises to fatigue the lower trapezius and
induce scapula discinesis.
The first study showed that healthy individuals and individuals diagnosed with shoulder
impingement can maximally activate the lower trapezius with specific prone shoulder exercises
(horizontal abduction of the prone at 130° with external rotation). This knowledge points to
important findings in the application of rehabilitation exercise prescriptions to shoulder
pathologies and scapula pathologies. The results of the second study showed the importance of the
lower trapezius in the dynamic movement of the normal scapula and the important contribution of
muscles to the scapula's discines. Interestingly, lower trapezius fatigue is a causative factor in
initiating scapula discinesia and may increase the risk of injury. Applying this knowledge to
clinical practice, a physician might assume that the lower endurance of trapezius may be an
important component in preventing injury to athletes above the head. This may lead to future injury
prevention studies to examine the effects of lower trapezius endurance programs on shoulder injury
prevention.
In addition, the results of this study have allowed further research to specifically target
rehabilitation protocols in scapula dyskinesis to determine whether overcoming the lower
trapezius can eliminate scapula dyskinesis and prevent future shoulder pathologies. This will be

115
breakthrough discovery because no other research has shown proper rehabilitation

116
Protocols for scapula discinetic and no research articles show a causal relationship to correct
abnormal movement patterns.

