


1
NOVEL REHABILITATION ROCKING CHAIR FOR TRUNK MUSCLE ACTIVATION
AND PATTERN ANALYSIS IN CHILDREN WITH SPINAL CORD INJURY
CHAPTER 1
INTRODUCTION
As in adults, spinal cord injuries (SCI) for pediatric patients are often
catastrophic, leading to dramatic changes in quality of life, overall health, and life
expectancy, not to mention the emotional and financial burdens carried by the families of
these patients. However, as younger SCI patients grow, additional medical complications
arise that are unique to this population due to musculoskeletal immaturity, i.e. the
patients are still growing. Conditions such as such as scoliosis and pneumonia can be
generally attributed to poor trunk control, a term used to describe the ability for a patient
to sit upright against the pull of gravity. Paradigm-shifting therapies such as locomotor
therapy (LT) have recently been developed as a mechanism to engage these patients in an
activity that enhances the quality of life for both adults and children living with SCI.
Therapies that improve trunk control, for pediatric SCI patients, is a critical therapy
target. As this dissertation will explore, LT has been shown to be a reliable method of
improving trunk control in a clinical setting. Extending the ability to make gains beyond
the clinic through the development of technology appropriate in the home environment is
the primary focus of this dissertation research project. In particular, this dissertation
outlines the development, evaluation, and analysis of a sensorized rocking chair designed
specifically for children with spinal cord injuries.

2
1.1 Project Goals
The goals of this multifaceted research project included: 1) the development of a
multi-sensor equipped prototype rocking chair for use by pediatric participants age 1-12
years with neurologic deficits that impair upright trunk control, 2) the characterization of
trunk muscle activation when children with SCI rock, 3) comparison of muscle activation
in TD children to muscle activation seen in children with impaired trunk control, 4)
characterization the output of sensors integrated in the rocking chair when children with
different levels of trunk control rock, and 5) the analysis of data produced by the rocking
chair sensors to find correlations between muscle group usage patterns, and to produce an
evaluation mechanism that clinicians can use to evaluate patient progress.
1.2 Project Specific Aims
To create a safe and engaging rocking chair for the pediatric patient population
that incorporates mechanisms to investigate and assess trunk activity levels in a manner
that is helpful to clinicians, this study has been broken down into four specific aims.
Aim 1: Design and fabricate an instrumented rocking chair for children with impaired
trunk control due to spinal cord injury and verify that it meets safety and operational
criteria.
This aim focuses on fabricating a rocking chair to provide therapists with a safe,
enjoyable method to enable trunk movement in children with impaired trunk control for
integration into activity-based therapy, or for use in increasing activity levels in the home.
Additionally, it will enable research to discover patterns of muscle activation during

3
rocking and can be evaluated for its ability to provide data which can be used in
assessment of trunk control in this population.
Aim 2: Characterize muscle activation in typically developing children and in those with
impaired trunk control while rocking in a rocking chair and describe differences
between muscle activation in the two groups.
This aim focuses on investigation of muscle activation during rocking in children
with SCI to determine if rocking activates muscles of interest, and to characterize muscle
activation patterns. This will help to investigate the hypothesis that rocking activates
trunk muscles, and to provide information about muscle activation timing in typically
developing children and children with SCI.
Aim 3: Characterize the relationship between rocking chair dynamics and Segmental
Assessment of Trunk Control (SATCo) score when children with different trunk control
capabilities rock.
This aim focuses on defining how the output of sensors changes when children
with different levels of trunk control perform the rocking activity, and identifying the
muscles in different domains (legs, arms, trunk) used during the activity. These will offer
insight into the mechanisms of how a child initiates and maintains the rocking activity
and will provide information which can be used to investigate other methods of
assessing trunk control.
Aim 4: Develop an algorithm to assess trunk control using data produced by sensors
on the instrumented rocking chair and evaluate its clinical utility.

4
This aim focuses on developing methods to utilize data collected from rocking
chair sensors to provide therapists with useful information about the child’s trunk control.
Regression analysis will used to find correlations between sensor data and trunk control,
and to produce a model for predicting SATCo score. If, however, after checking
correlations, there are not any independent variables which are well correlated with
SATCo other methods of data processing may be explored.
Successful completion of these aims sets the stage for future research to
investigate the clinical use of the chair both as a diagnostic tool (perhaps initially as a
confirmation of the existing SATCO assessment technique in the clinic), a tracking tool
(to monitor patient gains made through LT applied in the clinic), and possibly as a means
of applying activity-based therapy in the home environment.

5
CHAPTER 2
BACKGROUND
2.1 Demographics of Spinal Cord Injury
The National Spinal Cord Injury (SCI) Statistical Center, estimates that there are
currently 299,000 people living with SCI in the United States, with about 18,000 new
cases of SCI occurring annually [1, 2]. Of these, approximately 4-5% of are children at
the time of injury [3]. The most prevalent cause of pediatric SCI is motor vehicle
accidents (32%), followed by falls (18%) [4].
The economic impact of SCI can be devastating. SCI persons injured since 1970
spent an average of 171 days in a hospital over the first 2 years post injury [5]. In 2001,
Sekhorn et al reported that initial hospital expenses averaged $95,203, and $2958 per
year after initial recovery and rehabilitation. Other medical services and equipment
averaged $4,908 per year, and personal assistance costs and costs of institutional care
averaged $6,269 per year. In addition, loss of productivity and income are major factors
for consideration especially in the case of young people and children [6].
2.2 Spinal Cord Physiology
The spinal cord is the primary information pathway that receives sensory
information from the body and relays it to the brain. It also carries messages from the
brain to other body systems [7]. In addition to transmitting information, the spinal cord
actively processes information and generates motor outputs. Millions of nerve cells
collected into neuronal networks, referred to as the central pattern generator, are situated
6
in the spinal cord and coordinate complex movement patterns such as rhythmic breathing
and walking [8].
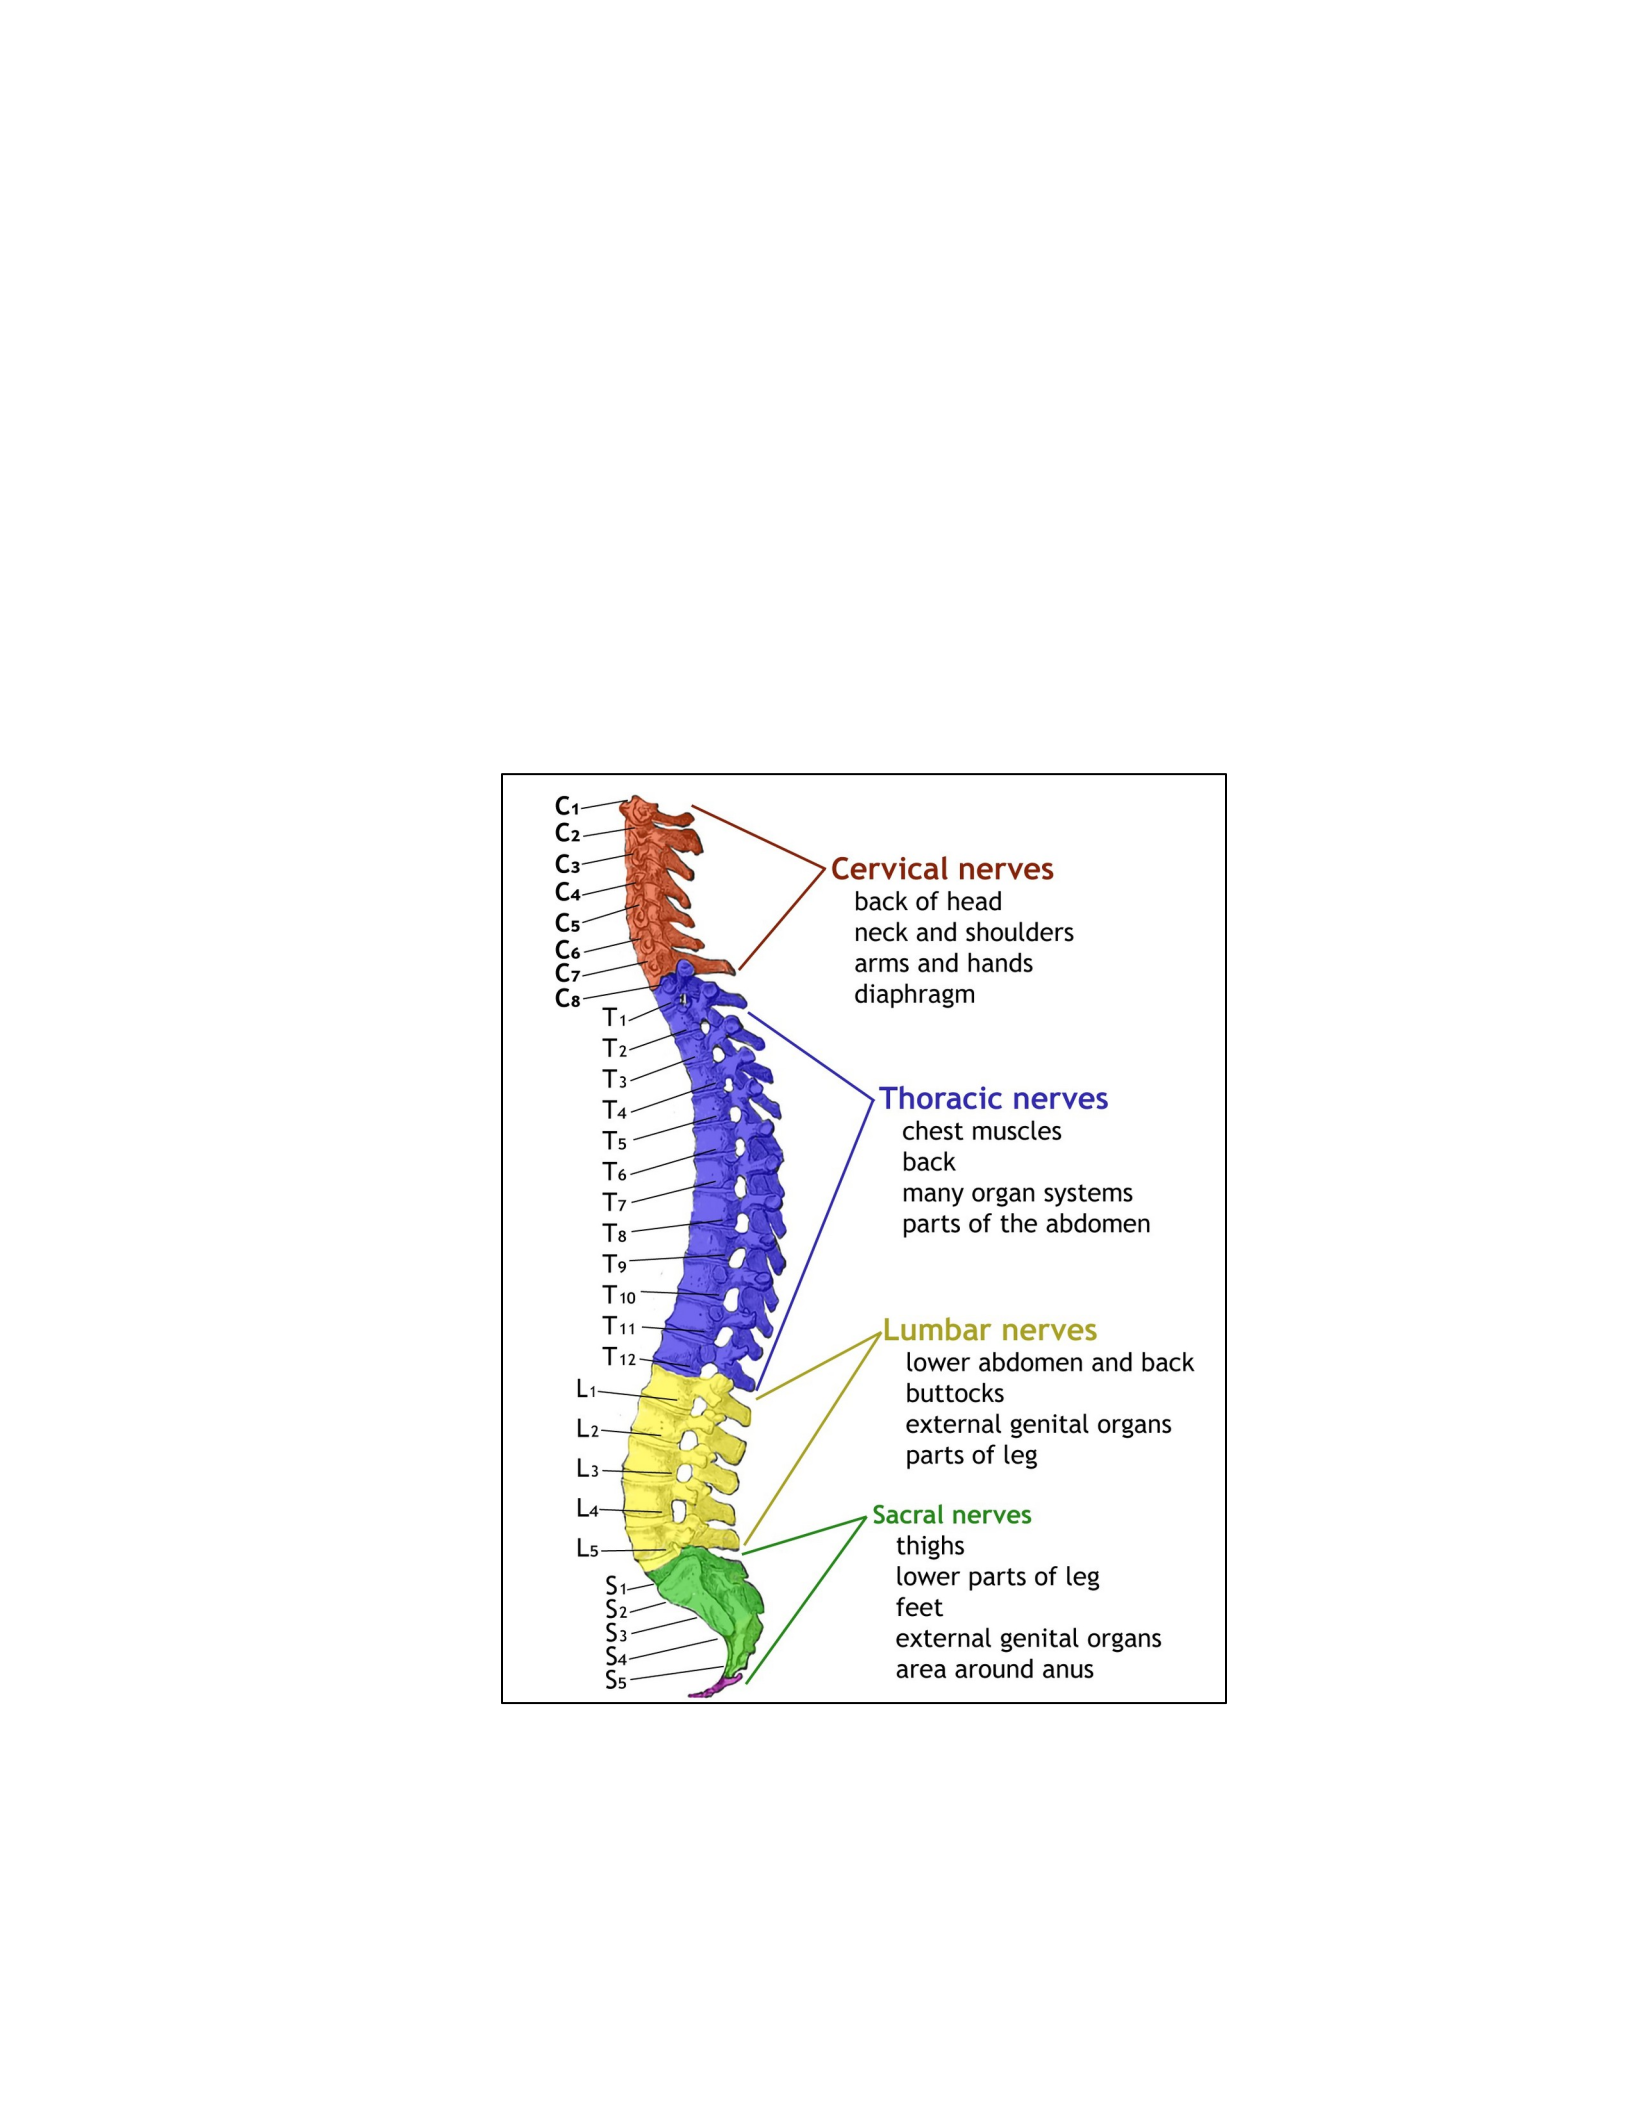
The spinal cord is linked to the muscles via spinal nerves which exit the spine at
different levels and nerve function is determined by the level as shown in Figure 1. The
cervical spinal nerves (C1 to C8) control the back of the head, the neck and shoulders, the
arms and hands, and the diaphragm; the thoracic spinal nerves (T1 to T12) control the
chest muscles, some muscles of the back, and many organ systems, including parts of the
abdomen; the lumbar spinal nerves (L1 to L5) control the lower parts of the abdomen and
Figure 1: Spinal nerve origins and functions
Adapted from Henry Gray, Anatomy: descriptive and surgical (1858)

7
the back, the buttocks, some parts of the external genital organs, and parts of the leg;
finally, the sacral spinal nerves (S1 to S5) control the thighs and lower parts of the legs,
the feet, most of the external genital organs, and the area around the anus [7].
2.3 Spinal Cord Injury
The most common and severe cause of spinal cord injury (SCI) is trauma.
Traumatic injuries (falls, etc.) often fracture vertebral bodies which can lead to
compression of the spinal cord, and associated permanent impairments including motor,
sensory and autonomic dysfunction. Other causes of SCI include inflammatory
conditions, infections, vascular issues, and neoplastic or degenerative changes [9]. The
nature and severity of dysfunction depends largely on the level of the spine at which the
injury occurs, and the degree to which the spinal cord is damaged [9, 10].
Failure to recover post injury leads to neurological disability and is the result of
axonal and other cellular damage, followed by regenerative failure and loss of
neuroplasticity, the ability of the nervous system to alter activity in response to stimuli by
reworking structure, functionality, and/or connections, in the region of the injury [9].
Recovery of function after injury depends upon the severity of neurological injury, with
cell and axon survival leading to proportionately improved recovery, and also the
neurological level of injury, with higher anatomical injuries leading to greater loss of
function [7, 10]. It has typically been believed that most neurological recovery in patients
with SCI occurs within the first 6 months after injury, but it has been established that
improvements can continue to occur years later [10].
8
2.4 Impacts of Spinal Cord Injury
The long-term effects of SCI are far reaching and affect almost every body
system, including respiration, head/trunk control, bladder control, speech, cardiovascular
function, and the musculoskeletal system [11]. Table 1 includes an abbreviated list of
conditions either caused by or aggravated by SCI and the prevalence in a cohort of
patients whose initial injury occurred during childhood [12].
Table 1: Common complications associated with SCI
Complications
Number with
complication
Number of
Respondents
Percent of
Respondents
Urinary tract infections 160 215 74%
Severe UTI 41 214 19%
Urinary stones 54 215 25%
Bladder incontinence 52 212 25%
Orchitis/ epididymitis 15 147 10%
Autonomic dysreflexia 85 157 54%
Hyperhidrosis 31 210 15%
Bowel incontinence 135 215 63%
Latex allergy 18 208 9%
Pressure ulcers 94 216 44%
Thromboembolism 41 216 19%
Respiratory complications 71 213 33%
Chronic medical conditions 42 214 20%
Other hospitalizations 59 215 27%
Adapted from Vogel et al 2002
2.5 Functional Impairments
In a survey of 681 adults with spinal cord injuries, 7 functions were ranked with
respect to which would most dramatically improve the respondent’s life if it was
regained. The functions included arm/hand function, upper body/trunk strength,
bladder/bowel function, sexual function, elimination of chronic pain, normal sensation,
and walking movement. Results showed that those with paraplegia ranked sexual

9
function and bladder/bowel function as the first and second highest priority, and those
with tetraplegia ranked arm/hand function and sexual function as the first and second
highest priorities. Regaining trunk stability was rated the third highest of the seven
functions most desired by both groups to improve their quality of life [13].
2.6 Spinal Cord Injury Rehabilitation
Physical rehabilitation, which is the primary intervention post-SCI for both adults
and children, has traditionally focused on management and compensation as the primary
solutions to combat impaired trunk control [14, 15]. Compensation in this context refers
to the use of assistive technology devices often specifically designed for SCI patients,
and management refers to medical interventions to treat medical conditions associated
with SCI.
Traditional approaches have involved the use of support mechanisms such as
thoracolumbosacral orthoses [16, 17], supportive and adaptive seating systems, cushions,
and chest straps [14, 18]. Additionally, practical techniques such as hooking an arm over
a wheelchair handle or positioning arms to create a stable base of support can help to
compensate for lack of trunk control [14]. These compensation-based strategies can help
the patient to engage in functional activities, but do not focus on neuromuscular
function. Moreover, by restricting movement they may contribute to deconditioning and
reduction in muscle mass, eventually leading to further impairment as neural circuits in
the spinal cord become inactive with disuse [19, 20].
Task specific, activity-based training methods have been investigated in adults
with thoracic SCI, to improve intrinsic trunk control by actively engaging the
neuromuscular system through sensorimotor input. Methods that have been studied

10
include kayak ergometer training [21], exercises that move the upper body outside the
base of support [22], and balance exercises performed on a rocker board which required
subjects to engage their trunk muscles to maintain balance and stability [23]. These
studies have demonstrated improvement in various functional measures of balance and
trunk control, and provide evidence that it is possible to improve intrinsic trunk control in
adults with SCI.
Recently, however, a new paradigm has emerged which promises the possibility
of restoration of at least some intrinsic neuromuscular control. In the context of a healthy
spinal cord, an input signal, which can be interpreted as the intent to perform a physical
action, is provided by the brain, and arrives in the central pattern generator of the spinal
cord via descending neural pathways. In the context of a compromised spinal cord, where
the descending pathways have been interrupted (corrupted, damaged, completely
severed), it has been shown that sensory input ascending to the spinal cord can instead (or
in place of the descending signal) stimulate motor responses, and that the spinal cord can
actually be retrained to respond by generating appropriate motor responses [24].
2.7 Pediatric Spinal Cord Injury
2.7.1 Trunk Control
Children with SCI experience many of the same consequences as those seen in
adults, but in addition to the impact of the initial injury, there are also debilitating
secondary consequences including altered growth and development as they mature [25].
In children as in adults, the long-term effects of SCI are far reaching and affect almost
every body system, including respiration, head/trunk control, bladder and bowel control,
speech, cardiovascular function, and the musculoskeletal system [11, 26, 27].
11
Skeletal immaturity and continuous musculoskeletal growth in the context of
impaired trunk control can also place children with SCI at substantial risk for developing
chronic conditions such as pneumonia, and scoliosis, a likelihood that increases the
younger the age of injury [3, 13, 17, 27, 28]. In a retrospective study by Dearolf et al, of
130 children with spinal cord injuries sustained before the typical adolescent growth spurt
(defined as age <12 years for girls and <14 years for boys), 97% developed scoliosis of
greater than 10 degrees. By way of comparison, only 48% of those injured after the
growth spurt developed scoliosis [17].
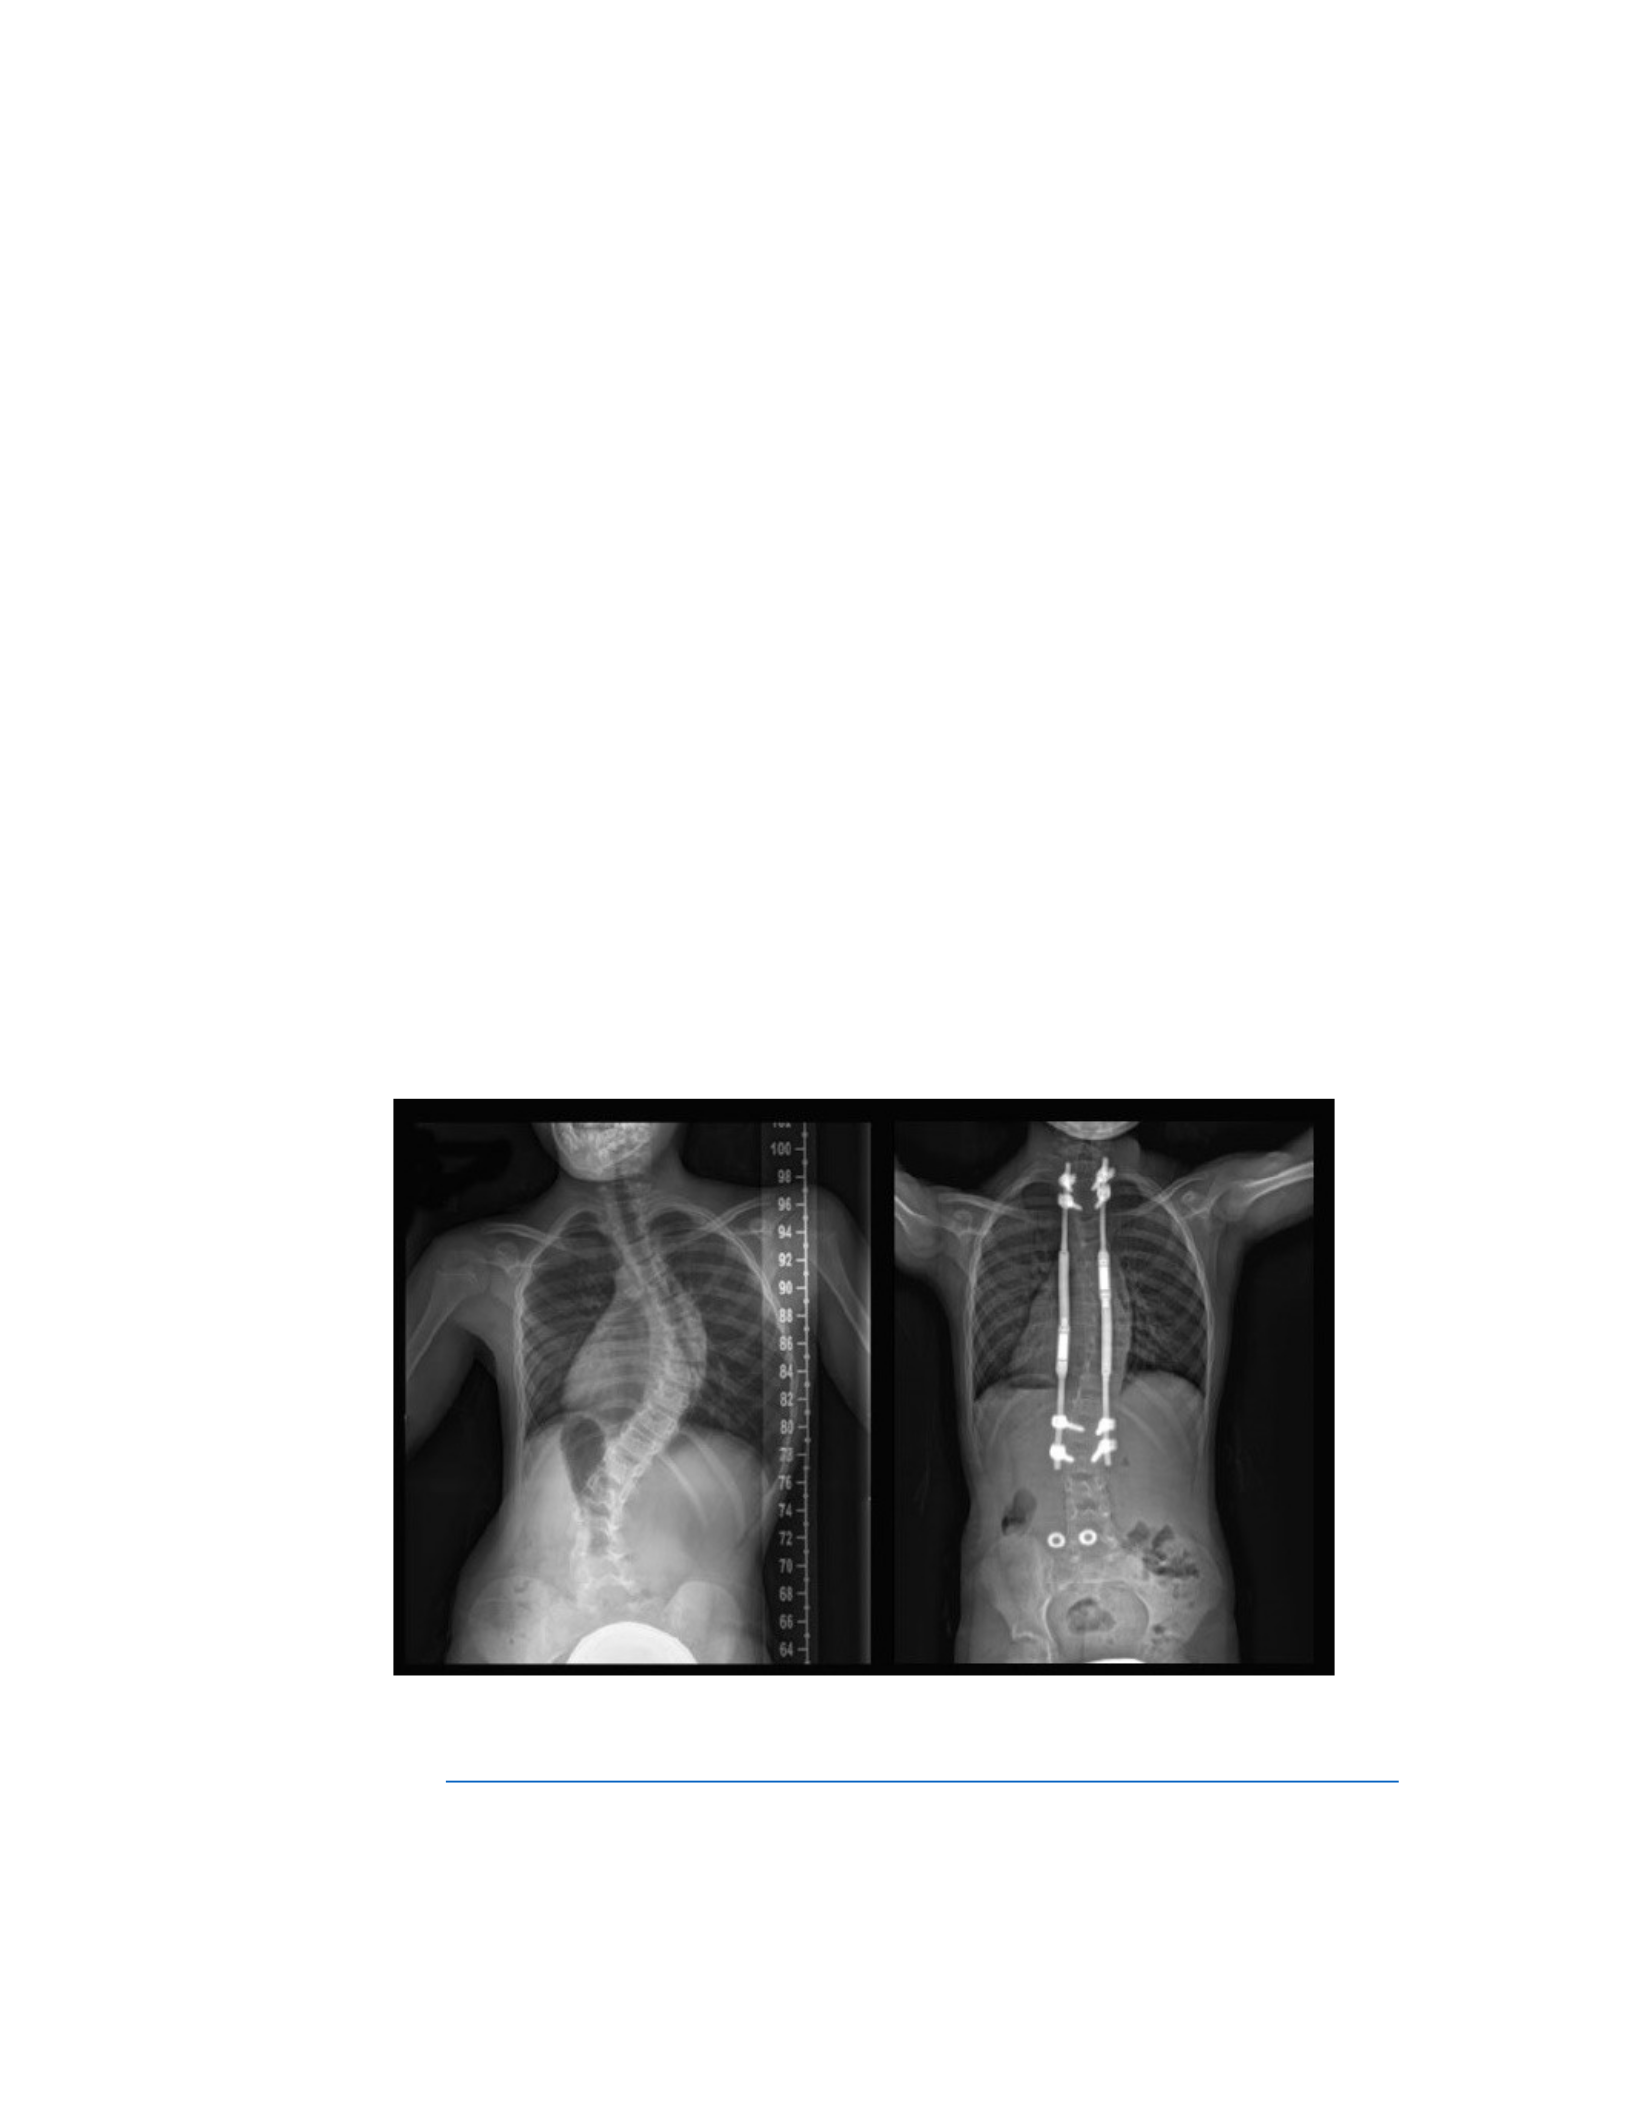
Surgical intervention to correct scoliosis (Figure 2) in particular, is a highly
invasive procedure that increased in cost from approximately $72,000 in 2001 to
$155,000 in 2011, with the cost of spinal implant mechanisms suggested as the primary
reason for the annual 11.3% increase [29]. Further, surgery to correct for scoliosis is often
Figure 2: Representative image of scoliosis, pre (left) and post-surgery (right).
Source:
pediatricscoliosissurgery.com/case-studies/meghan-pediatric-scoliosis-case/
12
repeated as a child ages, can result in further restriction of movement, and often interferes
with development of lung capacity in younger children [30].
2.7.2 Compromised Respiratory Function
Impairment of respiratory muscles in pediatric SCI can lead to respiratory
insufficiency [17, 28, 31, 32], and impairment of trunk muscles leads to the development
of neuromuscular scoliosis in most children who sustain SCI prior to skeletal maturity.
This can decrease the mechanical efficiency of the chest wall, further reducing lung
capacity and function [3, 28, 32]. Furthermore, due to years of immobility and lack of
weight bearing, pathophysiological changes in the musculoskeletal system progress, and
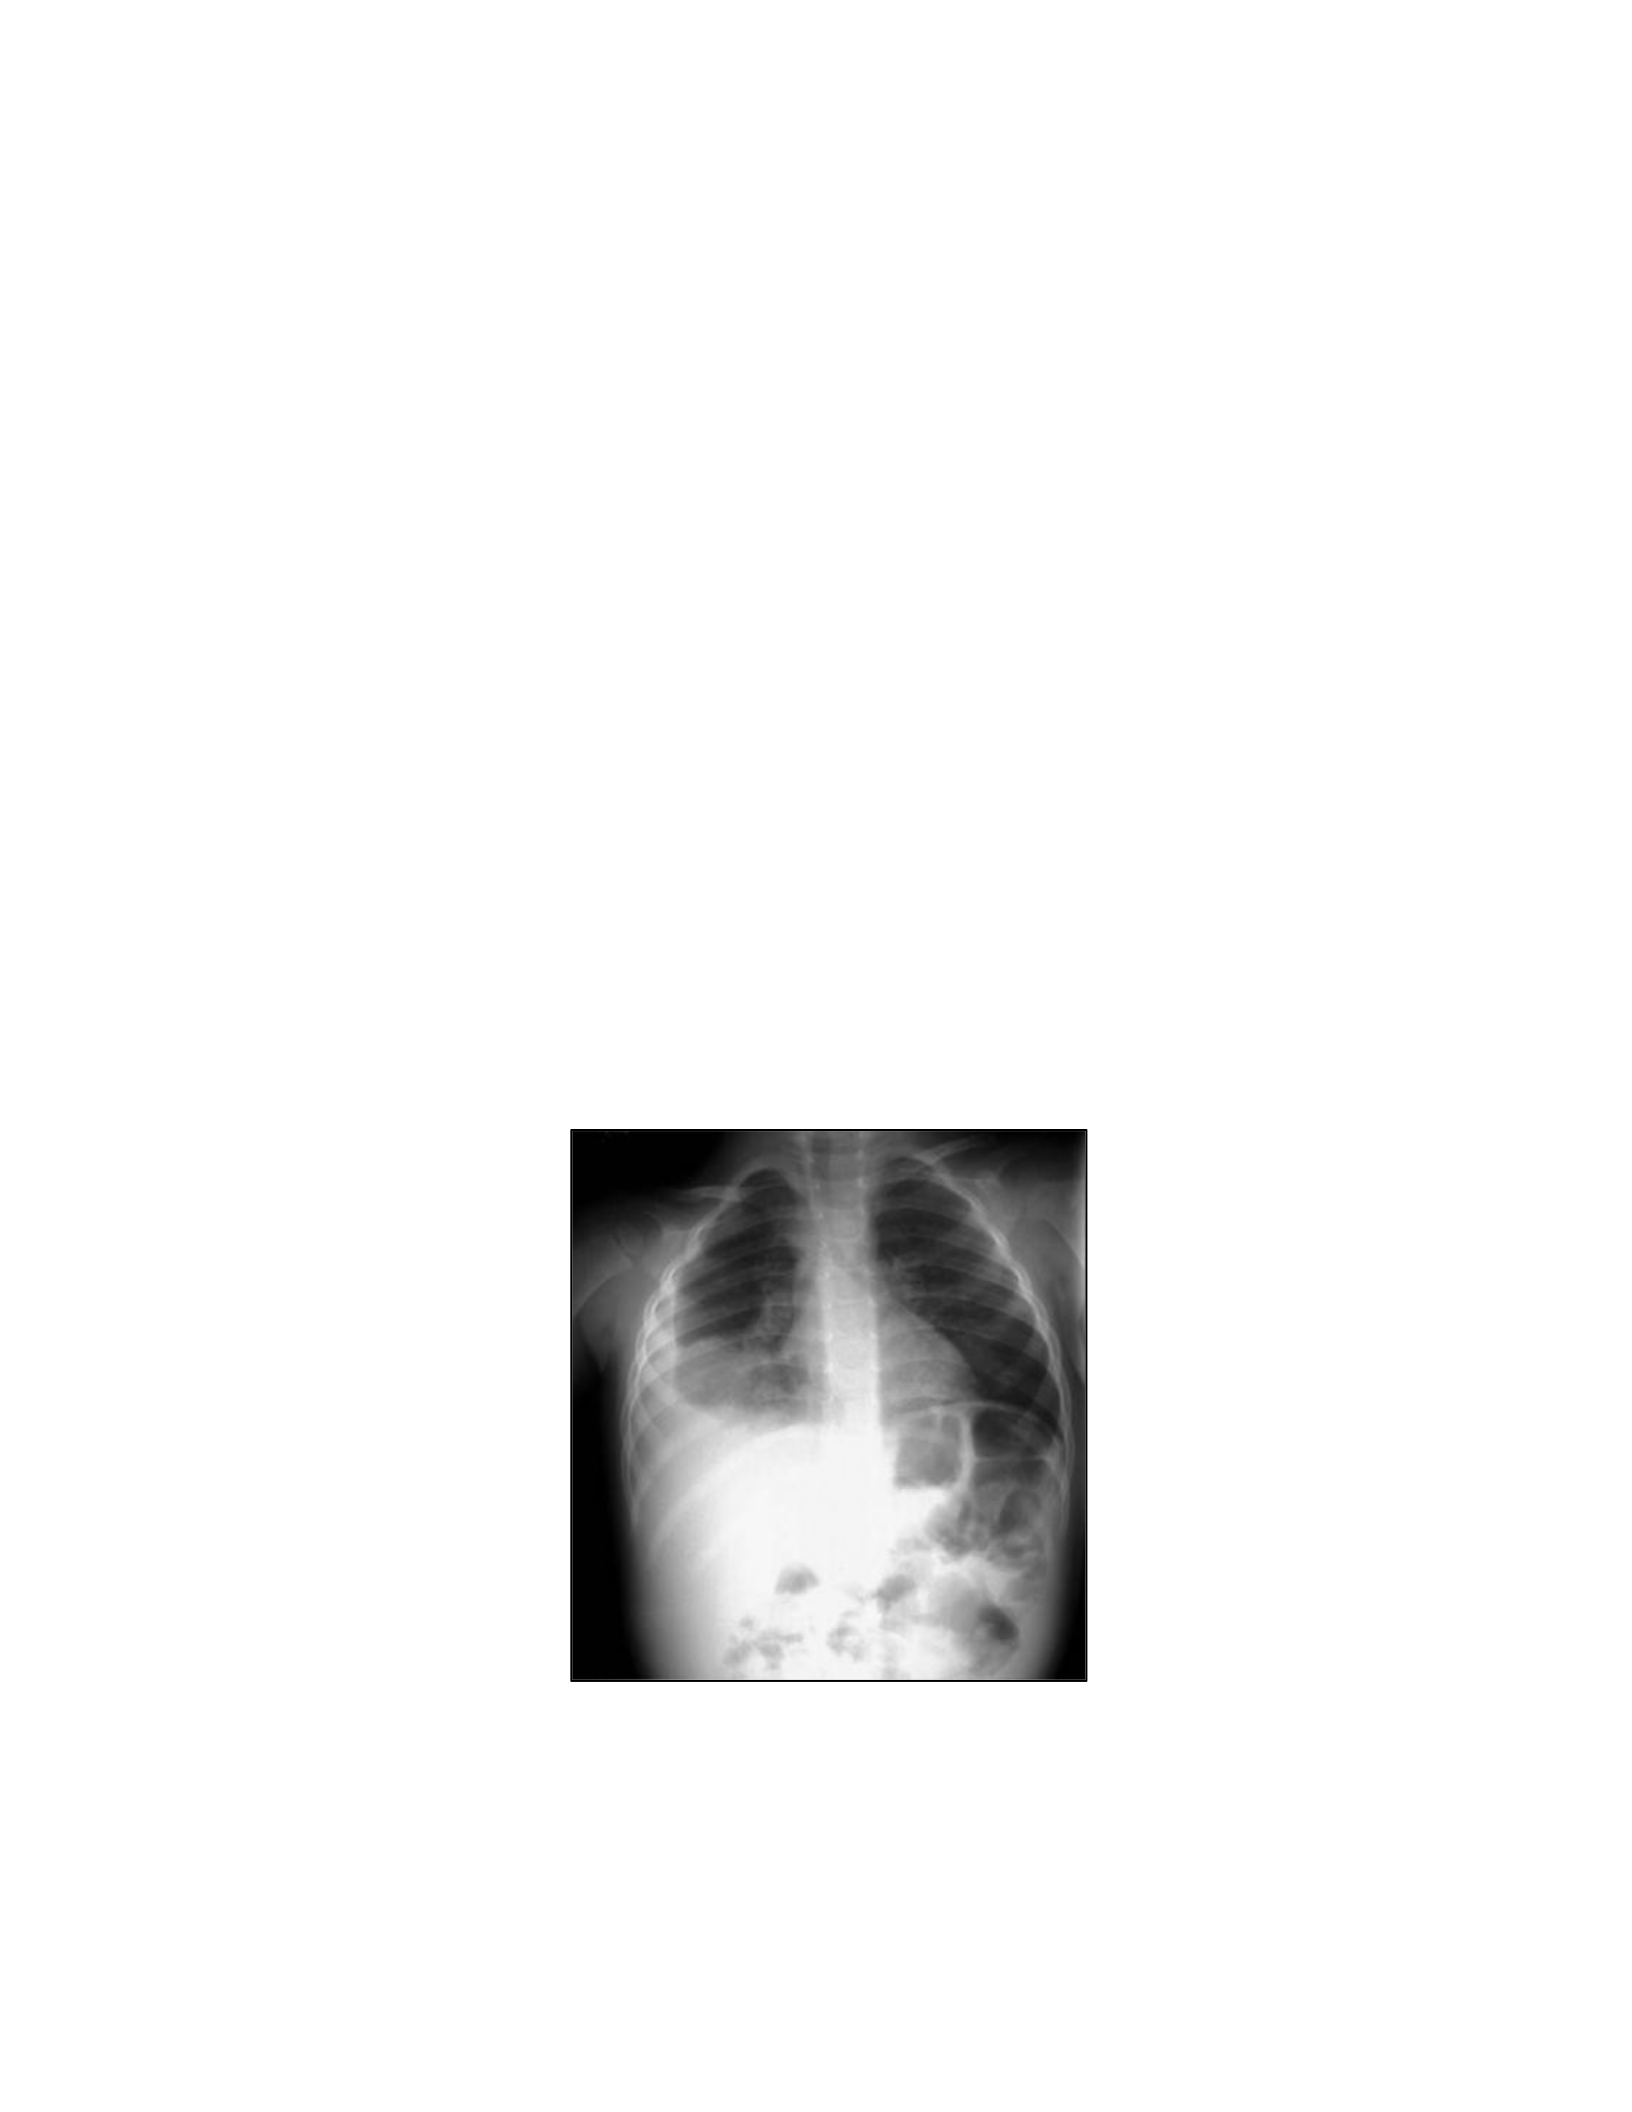
respiratory function is further compromised [27, 31, 32]. Respiratory insufficiency can
ultimately lead to complications such as infection, pneumonia (Figure 3) and even death
[32].
Figure 3: Image of bacterial pneumonia (right lobe of the lung)
Source: emedicine.medscape.com/article/967822-overview

13
2.7.3 Trunk Control Assessment
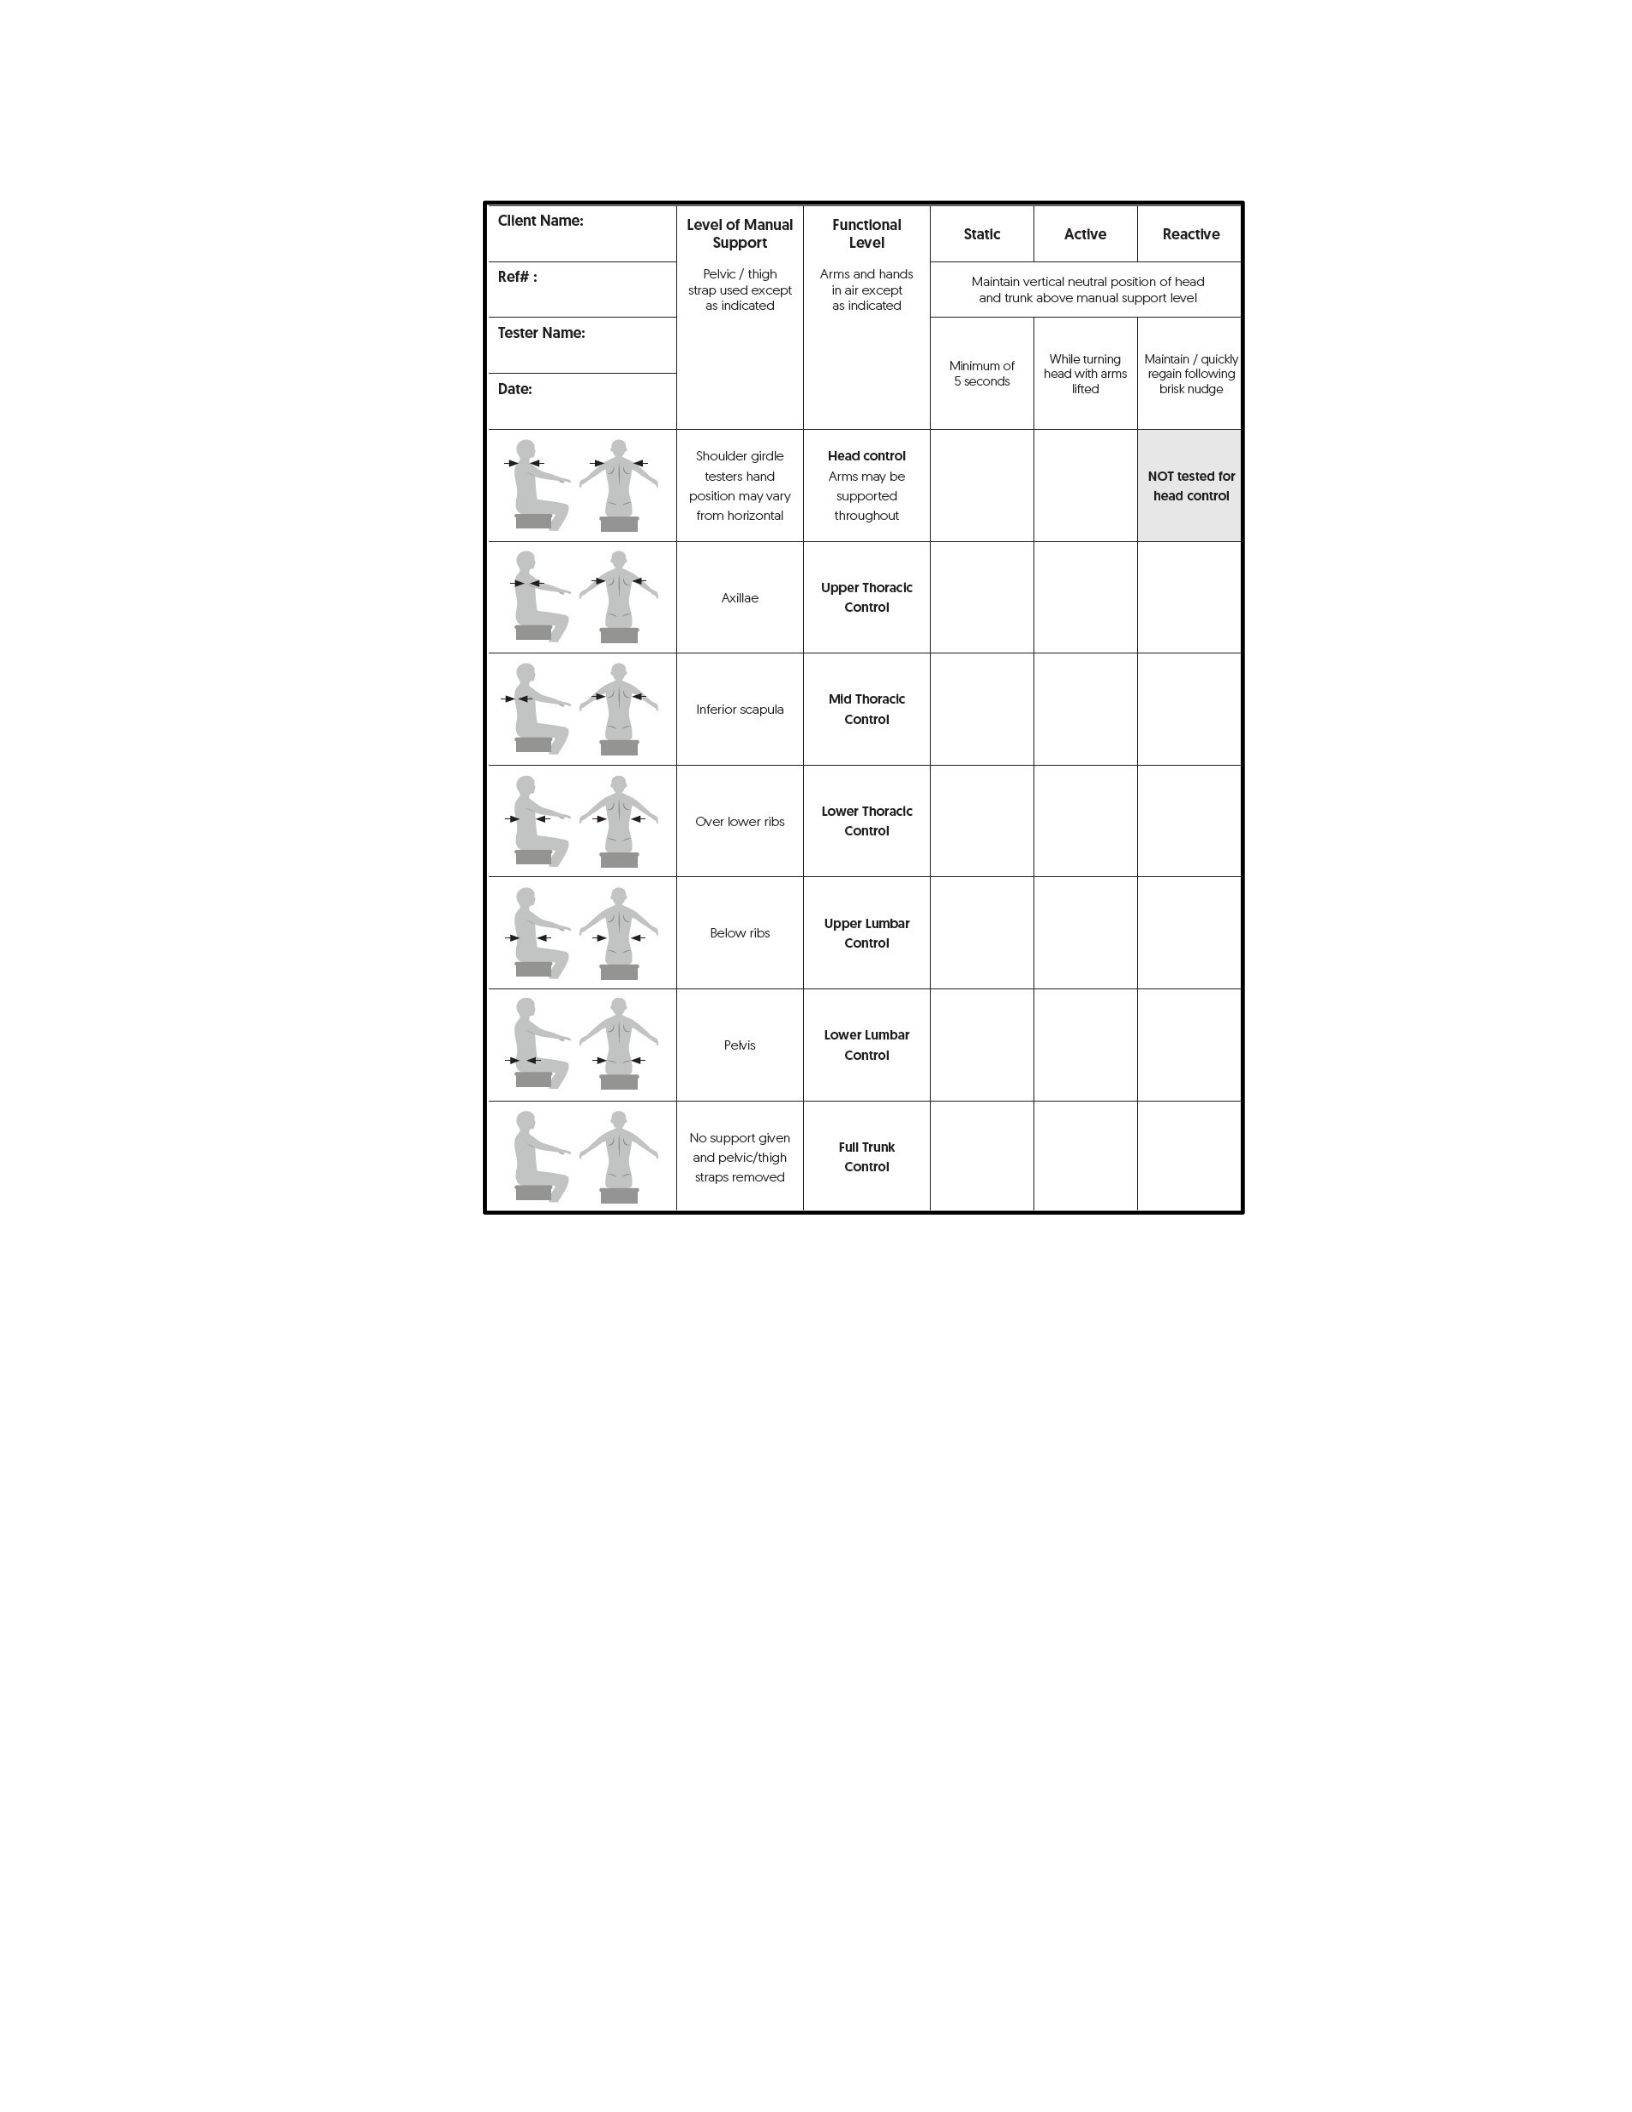
The Segmental Assessment of Trunk Control (SATCo) scoring tool was
specifically developed for use in pediatric populations to evaluate the trunk incrementally
across seven levels from shoulder support to no support and for three types of control
(static, active and reactive) [33, 34]. With each incremental level of external support,
trunk control above the location of support is evaluated across the control types and if the
child is deemed competent, the assessment continues until the child is unable to maintain
an appropriate sitting posture. A SATCo score of ‘0’ indicates no head control, whereas a
perfect score of ‘20’ indicates that a child can sit without any support and control their
head and trunk during static, active, and dynamic tests of control. Figure 4 shows a
SATCO assessment form designed for clinical use [35].
2.8 Rehabilitation
Various assistive technologies and therapeutic interventions have been used to
address impaired trunk control for children with SCI. During rehab sessions, patients
learn specific methods to compensate for their impairment. For instance, to balance and
sit upright by using counter-balance maneuvers with the arms and head above their
passive trunk and to establish an adequately wide base of support (i.e. posterior pelvic tilt
base). In some cases, the torso may be propped to a weight-bearing position using
extended arms. practical techniques such as hooking an arm over a wheelchair handle or
positioning arms to create a stable base of support can help to compensate for lack of
trunk control [10]. These compensation-based strategies can help the patient to engage in
functional activities, but do not focus on neuromuscular function.
14
Figure 4: SATCo testing procedure.
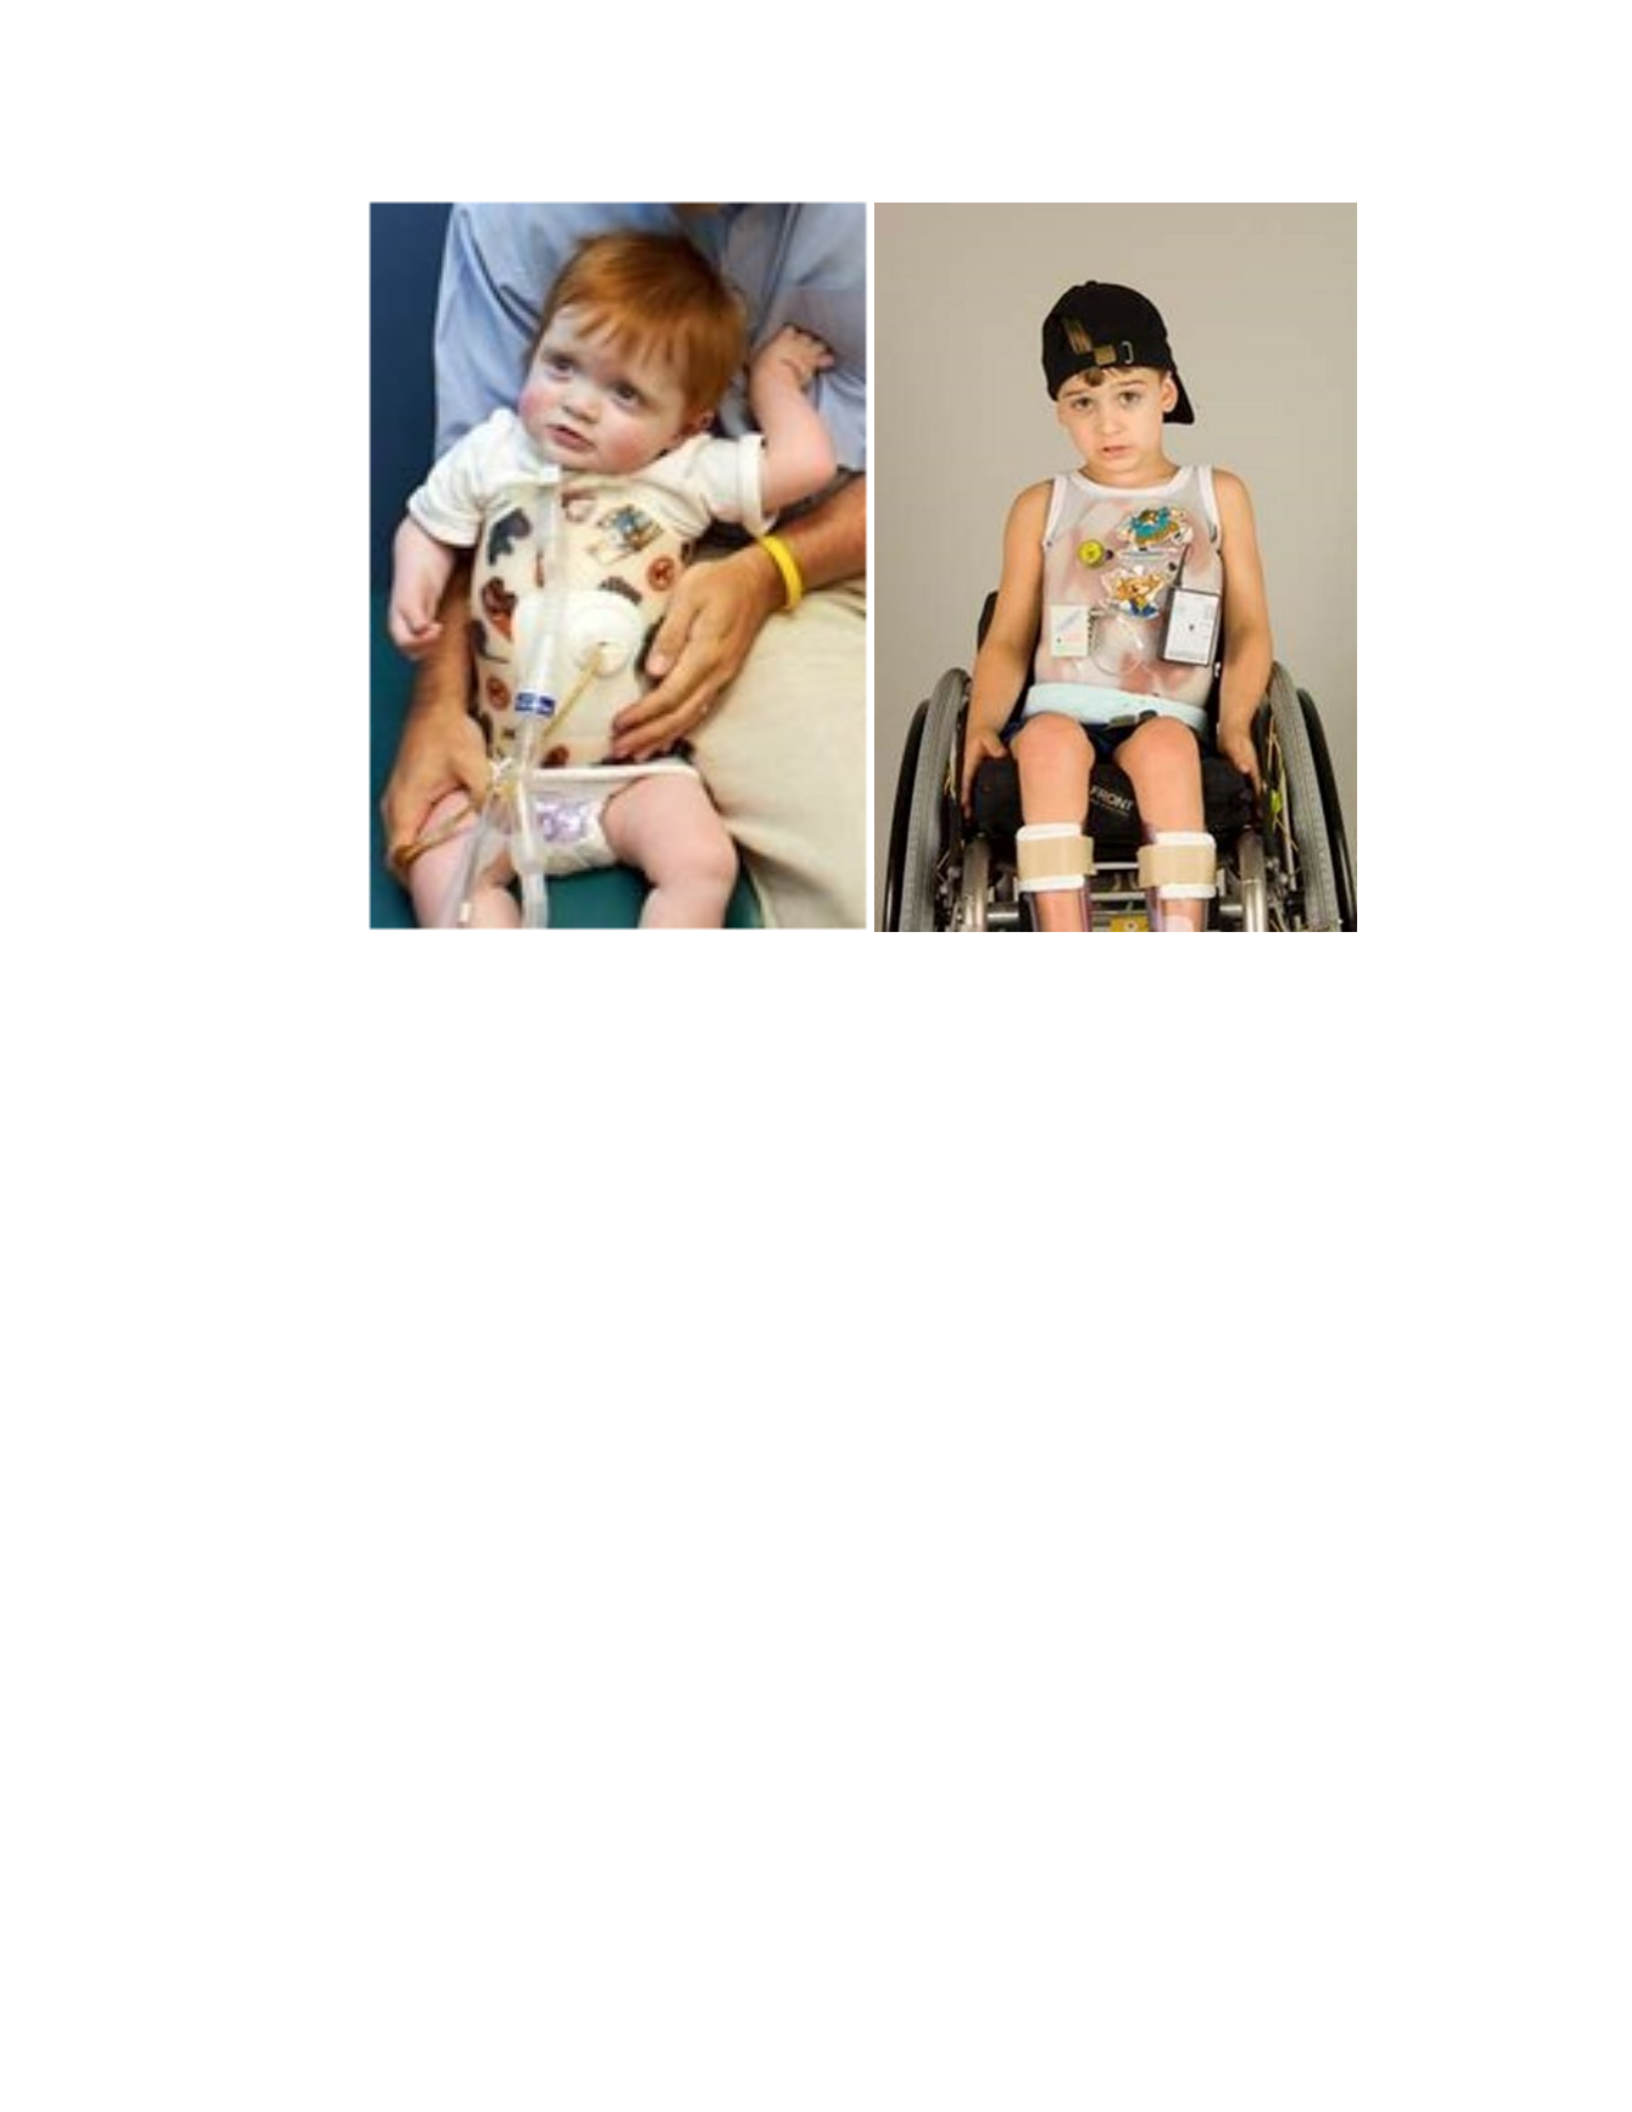
Rehabilitation interventions for children with SCI may also utilize devices such as
standers, wheelchairs with supportive and adaptive seating systems, cushions, and chest
straps [14, 18], and braces such as thoraco-lumbo-sacral orthoses (Figure 5) [16, 17].
While these devices provide support, many of them can also restrict trunk, leg, and body
movement. Medications to manage spasticity, such as botox injections and baclofen can
also add to paralysis, and further prevent movement [36]. By restricting movement some
strategies may contribute to deconditioning and reduction in muscle mass, eventually
15
Figure 5: Thoraco-lumbo-sacral orthoses
leading to further impairment as neural circuits in the spinal cord become inactive with
disuse [19, 20, 33].
From historical evidence and general clinical observation, pediatric rehabilitation
professionals do not expect or even suggest that therapeutic interventions promote or
restore trunk control in children post-SCI [33], and after 12 to 18 months post injury,
additional recovery is generally not expected, and parents are often given little to no hope
for recovery [36].
2.8.1 ABT for Children with SCI
Based on spinal cord neuroplasticity, a new field of therapy for SCI has emerged,
which is referred to as Activity-Based Therapy (ABT). Currently, in the pediatric

16
recovery-based program at the University of Louisville, the primary therapeutic
intervention for pediatric SCI subjects is activity-based locomotor training (AB-LT)
conducted 1.5 hours per day, five days per week with a targeted goal of 60 sessions over
roughly three months of therapy. Therapy sessions consist of a minimum of 55 minutes
on a walking treadmill equipped with active body weight support (BWS), where the
patient is assisted by four trained physical therapists, where the treadmill and body
weight support are integrated into the unit (Figure 6), providing therapeutic intervention
for SCI patients. The intervention delivered through use of the treadmill activity
provides task-specific sensory input that reinforces upright, appropriate alignment of the
trunk,
Figure 6: Pediatric locomotor training system.

17
Courtesy of Frazier Rehab and PowerNeuro Recovery.

18
pelvis and legs, weight bearing through legs, age-appropriate walking speeds, arm swing
and inter/intra-limb coordination of kinematics for both standing and stepping [36].
AB-LT therapy is followed immediately by 30 minutes of assessment by the
therapists and clinicians as well as off-treadmill activities that further emphasize and
reinforce the gains attained/observed from repeated application of the specialized
training. These extended activities promote active trunk extension or rotation by placing
balls or toys overhead or to the child’s side for them to reach for and grasp. Postures that
minimize use of compensation are also encouraged by having children shoot baskets or
carefully remove pieces of a puzzle tower while maintaining a stable trunk. Encouraging
children to use postures such as arms in contact with the body or arms extended behind
the body can also help to minimize compensation [37, 38].
2.8.2 Trunk Control Improvements with ABT
In children with SCI, research has shown that activity-based locomotor training
(AB-LT), which provides sensorimotor input to activate the neuromuscular system,
leads to improvements in intrinsic trunk control as measured by SATCo score.
Significant changes in SATCo scores (p <0.0001) were determined for all participants
from initial to post-60th session evaluation [33, 34]. This improvement is observed
regardless of the chronicity or severity of the initial impairment, with similar
improvements seen in cervical, and in high and low thoracic injury [33]. These findings
align with case studies that support the notion of sensorimotor input playing a crucial
role in enhancing trunk control in children with SCI [39-41].

19
2.9 Rocking Chair to Activate Trunk Muscles in Pediatric SCI
Studies demonstrate that improving intrinsic trunk control in subjects with SCI is
possible [21-23, 33, 39-41]. There is need, however, for methods to reinforce and
maintain these gains in trunk control through community integration activities that allow
patients to continue to extend their capacity via the retrained nervous system in the home
and community [21].
One activity that researchers have explored is the act of rocking in a rocking
chair, which enables a user to generate movement with minimal or no caregiver
assistance. In one case study, a pediatric rocking chair was adapted for a 3-year-old with
a cervical spinal cord injury to allow for weight bearing through the feet with upright
posture and engaged muscle activation in both the arms and the trunk [19]. The
periodicity of motion created by rocking and the requirement of an upright posture to
initiate and maintain the rocking motion equally promote an accessible, self-initiated, and
engaging activity for children of all ages, including those patients who have limited
capacity to move and interact with their environment. Rocking would seem then to
complement and reach beyond clinically delivered, activity-based therapies such as
locomotor training.
Clinically derived improvements in trunk control could be safely practiced by providing a
home-based, age-appropriate, and accessible activity that encourages repetitive activation
of the muscles associated with trunk control. Additionally, enjoyment of an activity is an
important motivator for children which results in increased time/practice engaged in the
activity, and in turn accelerates improvement and lasting use. To study the benefits of
rocking, however, it is necessary to design a rocking chair that meets the particular needs
of this population.

20
2.10 Rocking Chair Therapy Review
Rocking chairs have been investigated for their effectiveness in several domains,
including postoperative recovery, enhancing physical function in the elderly, workplace
ergonomics, and emotional regulation in substance-use disorder. Investigation of the
effects of postoperative rocking revealed improvement in several measures of recovery
including postoperative ileus duration and [42, 43] and time to first flatus [44].
Research on the use of rocking by elderly people showed improvements in
physical performance as measured by the Berg Balance Scale, maximum knee extension
strength, and maximum walking speed [45]. Other work has shown activation of the
rectus abdominis during rocking, and improved rectus abdominis strength in elderly men
as measured by number of sit-ups completed after six weeks of rocking chair use [46].
Pierce et al. observed a rise in blood pressure among hypotensive older adults during
rocking, which suggests that rocking may improve cerebral perfusion in older adults with
hypotension and thus help to slow Alzheimer’s disease (AD) progression or improve
function of AD patients [47].
Udo et al. examined the effects of rocking on pain and discomfort during seated
work in an office environment, and found a significant decrease in pain in the neck,
shoulders, back and lower back, but an increase in hip pain [48]. Cross et al performed a
study involving veterans with substance use disorder and concluded that vestibular
stimulation through rocking chairs might help self-regulate mood and cravings,
potentially reducing relapse risk [49].
There were no studies found in the current literature that applied or investigated
the use of rocking chairs in the context of pediatric SCI.

21
2.11 Instrumented Rocking Chair to Monitor Muscle Activation
In addition to providing a way to allow children with SCI to activate trunk
muscles in the home, a rocking chair specifically designed for children with impaired
trunk control and instrumented with sensors, would provide researchers and clinicians
with an opportunity to collect data about the characteristics of the rocking activity, and
such a device may be able to provide information about muscle activation and progress in
trunk control. A quantifiable method of collecting data which could be utilized on an
ongoing basis to assess and track changes in muscle activity would be highly beneficial
to clinicians. Additionally, if data could be collected to allow the tracking of activities
and trunk control in the home, clinicians would have a better picture of patient activity
levels beyond the clinic, as well as an added dimension to the assessment of progress.
2.12 Existing Technology to Activate and Assess Trunk Muscles in
Pediatric SCI
A thorough search of both relevant literature and commercial equipment offerings
does not reveal the availability of rocking chair-based therapy tools for pediatric SCI
patients. Additionally, there are no instrumented devices that have been designed to
capture biometric data for purposes of assessing muscle activation in this patient
population. These gaps in the technology provide a clear opportunity to develop a system
to potentially provide a solution for both consumer and clinical use to extend the benefits
of ABT beyond the clinic, while providing researchers and clinicians insight into muscle
activation enabled by LT.
There are, however, products on the market that look to promote the use of trunk
muscles by individuals with SCI. One example is the TherAdapt Wheelchair Platform

22
Rocker (TherAdapt Products Inc, Ludington, Michigan, USA), shown in Figure 7 (left),
which is an add-on base to a standard wheelchair that allows a patient to increase their
activity level through rocking [50]. Traditional rocking chairs are also available,
however, as noted previously, these must be modified for use by children with SCI and,
even after modification, significant safety concerns and practical limitations exist.
Other therapy devices designed to provide trunk exercise are available
commercially. One example is the Meerkat stander (Etac AB, Torrance, California, USA)
shown in Figure 7 (right). This device is a standing frame which supports an upright
standing position for children needing varying levels of support. The central column can
be positioned in front of or behind the child and support can be adjusted to meet
Figure 7: TherAdapt Wheelchair Platform Rocker (left), and Meerkat stander (right)
Sources: www.theradapt.com/store/ShowProduct.aspx?ID=118;
www.etac.com/en-us/us/products/pediatrics/standing/r82-meerkat/

23
individual needs. To encourage movement, the base can be set up with wheels or an
optional rocker base which provides a mechanism to develop posture control [51].
None of the devices reviewed incorporate sensors to provide information to assess
use of the device or track improvements in trunk control.
2.13 Dissertation Organization
Chapter 1 has introduced the project and provided an outline of the specific aims being
pursued.
Chapter 2 has provided an overview of the issues involved with pediatric SCI, trunk
control, and ABT necessary to an understanding of the motivations and techniques
used in this project.
Chapter 3 will cover the methods used to achieve Aim 1 and the outcomes obtained. The
objectives that have been pursued to achieve this aim are:
Objective 1: Design of a rocking chair for children with SCI using a Quality
Function Deployment (QFD) process.
Objective 2: Fabricate the rocking chair.
Objective 3: Experimentally verify safety and operation of rocking chair.
Chapter 4 will focus on the methods used to achieve Aim 2, and describes the activities
undertaken to achieve the following objectives:
Objective 1: Characterize muscle activation while rocking for typically developing
children and children with impaired trunk control.
Objective 2: Describe the differences between muscle activation for
typically developing children and those with impaired trunk
control.

24
Chapter 5 will focus on the methods used to achieve Aims 3 and 4, and describes the
activities undertaken and results obtain in the completion of the following
objectives:
Objective 1: Characterize the changes in 1) applied forces on footrest, seat and
armrests, and 2) kinematics such as frequency, amplitude, and
accelerations, when children with different trunk control
capabilities rock.
Objective 2: Produce a model to predict patient’s trunk control capabilities.
25
CHAPTER 3
ROCKING CHAIR DEVELOPMENT
Introduction
The methodology chosen for the design of the rocking chair for children with SCI
is the quality function deployment (QFD) design process, a quality system that was
originally developed in Japan in the 1960s and has now been adopted by major
corporations worldwide. It is used to translate the needs of the end user (often referred to
as “needs of the customer”) into specific design characteristics and to implement these
characteristics in the design of the finished product [52]. The QFD process begins by
identifying the needs that the design should meet. This is accomplished by gathering
information from stakeholders about the specific needs and priorities for the product. This
information is then used to develop specific design features and requirements, which are
prioritized using tools like the House of Quality (HOQ) matrix to link them to the
importance of each of the needs identified earlier. Multiple alternative design concepts
that address the prioritized design requirements are developed and evaluated for how well
each alternative fulfils the identified needs. A detailed design is then developed based on
the selected concepts and drawings are created, materials are specified, and the
manufacturing processes are determined. Based on this design, a prototype is fabricated
and tested. Test procedures are designed to evaluate how well the prototype meets the
needs originally identified. This helps to validate the design, identify any potential issues,
and gather feedback for further improvements. The design may then be iterated until any

26
identified issues have been addressed. This design method can also be extended into the
manufacturing and distribution of the product to ensure that the manufactured product
continues to meet the standards set by the prototype build, and that it actually meets the
needs of the end users [53].
The aim of this study is to apply these engineering design methodologies to the
design, fabrication, and evaluation of a rocking chair that will meet the needs of children
with SCI and will allow for further study of the effects of rocking in this population.
Materials and Methods
3.2.1 Design Process
The initial phase of the QFD methodology involved identifying the fundamental
needs that the rocking chair should address. To accomplish this, a focus group discussion
was conducted with five therapists experienced in working with children in the target
demographic. Prior to the discussion, important topics to cover were identified, and a list
of questions designed to elicit information about needs the chair should meet was
produced. During the session, open-ended discussions were encouraged to allow
participants to identify needs without biasing them towards any predetermined
conclusions. As discussion progressed, the list of topics and questions was referenced to
ensure that all important issues had been addressed, and any pertinent questions were
asked. Conversation moved from general needs to more specific ones, and finally to the
suggestion of specific features to meet the identified needs. The needs identified during
the meeting were captured through notes taken on a pen board, and through audio
recordings which were reviewed later to ensure that no needs had been missed. The
identified needs were then compiled into an online form which the therapists filled out to

27
rate the importance of each need on a scale of 1 to 10. This ranked list of needs was used
to develop potential features and design requirements for the rocking chair.
When considering the design and setup of the rocking chair, it was also important
to take the anthropometric characteristics of the intended users into consideration.
Anthropometric data was collected from 22 children in the target population and was
used to define design targets that would ensure that the rocking chair would fit the
intended population of users.
The primary anthropometric measures considered in defining rocking chair design
targets were popliteal height (PH), buttock to popliteal length (BPL), and weight. PH is
the measurement from the bottom of the foot to the back of the thigh just above the knee
while sitting [54], and the range of PH in intended users is closely related to the range of
adjustments that can be made to the footrest height. BPL measures the length from
behind the buttocks to the back of the lower leg, just below the knee while sitting [54],
and helps to determines the required seat depth. Seat depth is measured from the front
edge of the seat to the backrest, and too deep of a seat can interfere with free movement
of the legs during rocking, and so is specified in terms of the maximum allowed depth.
These needs, features and design requirements were incorporated into a “House of
Quality” (HOQ) matrix which provides a structured approach for correlating customer
needs with specific design features. Based on the results of the HOQ matrix, a design was
created incorporating the features deemed important for addressing the needs of children
with SCI, and solid models, accurately representing real-world geometries for all
individual rocking chair parts, were generated using SolidWorks (v2020, Dassault

28
Systèmes SolidWorks Corporation, Waltham, MA). An assembly using these parts was
created to study chair dynamics and to perform stress/loading analysis.
3.2.2 Simulation Using the Finite Element Method
To assess the design, several simulation techniques were employed to validate its
performance. Motion studies that incorporate real-world physics were developed in the
virtual computer model to evaluate the rocking motion and stability of the chair. To
evaluate the structural integrity of the design, finite element analysis (FEA) was also
performed (SolidWorks Simulation V2020). For wood-based furniture products,
Eckelman recommends that the ultimate strength of wood members be reduced by 2/3 to
account for manufacturing variations such as defects and humidity [55]. The mechanical
properties of Baltic Birch plywood are anisotropic and therefore depend on the
orientation with respect to surface grain. For safety, the lowest reported values
(perpendicular to the face grain) of 3.58 x 10⁷ N/m2 for tensile strength, and 2.48 x 10⁷
N/m2 for compressive strength were used [56]. In the FEA analysis, these values were
reduced to 1/3 of the rated strength, or 1.19 x 10⁷ N/m2 for tensile strength and 8.27 x 10⁶
N/m2 for compressive strength. The factor of safety (FOS), which is a ratio between
ultimate stress of the material and the maximum working stress expected to be seen
during normal use, was used to evaluate the design at each iteration. An FOS of 1.5 is
typically used when evaluating reliable materials in conditions that are not severe (i.e.
high temperatures, wet conditions, etc.) [57].
To simulate a worst-case scenario (an individual much larger than the intended
user of the chair) the model was loaded with 136 kg (300lb) applied to the seat of the
chair, and factor of safety and deflection plots were generated.

29
Fabrication
Parts for the rocking chair were cut from Baltic birch plywood on a Computer
Numerical Control (CNC) router (ShopBot Tools, Inc. Durham, NC), with tool paths
generated based on the validated solid model. Other miscellaneous parts and hardware
(nuts, bolts, etc.) were purchased from commercial sources, and the chair was assembled,
wood parts were sealed with lacquer, and painted with ocean scenes.
Rocking Chair Mechanical Testing
3.4.1 Tipping
The base of the chair was blocked to allow the chair to tip instead of sliding on
the floor when a force was applied. The chair seat was then loaded with plate weights
(59 kg [130 lbs.], the maximum expected weight of patients in the target population), and
a horizontal force was applied at the top of the seat back. To apply and quantify this
load, a rope was tied to the top of the backrest of the chair, and a luggage scale
(American Tourister Travel luggage scale, 38 kg capacity - Model# AT97-635-027-61)
was attached. The scale was then pulled horizontally in the desired direction until the
chair reached the point at which it would continue to tip over (“tipping point”) if not
restrained. The maximum force exerted, and the lift height of the lifted side at the tipping
point were recorded, and the angle at which the tipping point was reached was
calculated. This was repeated for five repetitions each in forward, backward and side
loading configurations.
3.4.2 Maximum Load Testing
The ability of the chair to support greater than the maximum expected load was
also evaluated. For this test, 136 kg (300 lbs) of weights (representing 2.3 times the

30
maximum expected load) was placed on the seat of the chair and the chair was rocked
gently. The chair was then examined for any evidence of damage or weakness such
as cracking or bending of wood elements or fastener pull-out or deformation.
3.4.3 Strength and Stability Testing
Chair strength and stability in the expected range of dynamic loading were tested
with loads of 11 kg (25 lbs), 35 kg (78 lbs), and 59 kg (130 lbs). For these tests, weights
were placed on the seat of the chair and the chair was rocked manually to reach the
maximum possible travel amplitude (the safety stops included in the build effectively
limited maximum travel). During rocking, observations were made to identify signs of
weakness or instability; if tipping was observed, the height that the feet lifted off the floor
was recorded, and the angle of tilt was calculated. After loaded rocking, the load was
removed, and the chair was thoroughly inspected for any signs of damage or weakness as
mentioned previously.
Results
3.5.1 QFD Results
The QFD design process identified needs which fell into four categories. The
highest rated category identified by the therapists was safety, followed by therapeutic
needs, practical and aesthetic aspects, and a need for data to characterize and track the
child’s rocking. Table 2 and 3 show the categorized needs along with the importance
rating each need was assigned and design features proposed to meet that need.
Table 2: Customer requirements and features determined from focus group with physical
therapist (Safety and Therapeutic Need). Ratings on a scale of 1 to 10 and are averaged
for each category of needs.

31
Customer Needs Rating Proposed Design Features and Testing
Safety
Stability/strength 10.0 Baltic birch plywood construction; comprehensive strength/safety
testing
Secure child in the chair 10.0 Belt/Harness to secure child in seat
Resist tipping 9.8 Glider Style rocker with stable base; safety stop to limit range of
motion
Protect skin 10.0 Padding on seat, seat back, and armrests
Ability to lock rocker 8.0 Mechanism to prevent rocking during transfers etc.
Therapeutic Needs
Enable independent
movement
10.0 Means to position strap for adequate support while allowing as
much trunk motion as possible
Provide support 9.8 Full back, armrests, and straps to secure and support child
Engage leg muscles 9.8 Footrest attached to base to allow children to push with legs
Engage arm muscles 8.3 Armrests for child to push/pull on
Engage Trunk muscles 9.5 Removeable footrest; footrest attached to seat rather than to base
Increase vestibular
stimulation
4.0 Adjustable mode of rocking
Increase sensory
stimulation
6.3 Adjustable mode of rocking; Rocking inherently induces sensory
responses from multiple sense modalities (skin, muscle stretch
sensors,
vestibular
etc.)
Several features were chosen to meet the need for safety. These include the
implementation of safety stops to restrict the chair’s range of motion, padding to prevent
chafing and skin breakdown, the utilization of straps to securely hold the child in the seat,
the mitigation of potential pinch points, and a wide, stable base to prevent tipping.

32
Table 3: Customer requirements and features determined from focus group with physical
therapists (Practical Aspects/Aesthetic Appeal and Data for Assessment). Ratings on a
scale of 1 to 10 and are averaged for each category of needs.
Customer Needs Rating Proposed Design Features and Testing
Practical Aspects/Aesthetic
Appeal
Sized for target population
(age 1-12; up to 59kg)
8.8 Demographics of target population consulted when sizing chair
features (seat width, depth, footrest location and adjustment
range)
Adjust to fit child 9.8 Adjustable footrest; interchangeable seats; adjustable seat
position (larger seat)
Fit into home aesthetics 8.3 Seats made from commercially available child-sized chairs
Attractive to child 8.5 Painted with attractive ocean scenes
Ease of Transport 8.3 Built in wheels; handles for pushing/carrying; mechanism to
prevent rocking
Useable in multiple contexts 6.5 Detachable work surface; mechanism to prevent rocking for use
in other contexts
Fun for the child 9.3 Adjustable modes of rocking to determine which is most
enjoyable/most effective; ocean scenes painted on rocker to
stimulate child's imagination
Ease of use 9.3 Make similar to traditional rocking chair. Straps to hold feet on
footrest
Data for Assessment
Capture Rocking
Characteristics
6.3 Sensors to measure forces applied to chair surfaces
Muscle Activation Assessment 7.8 Data analysis algorithms to find correlations with muscle
activation
Trunk control Assessment 7.5 Data analysis algorithms to find correlations with trunk control
User-friendly display of data
7.5
Wi-Fi link to sensor data/LabVIEW data capture software
Features selected to address therapeutic needs include a full chair back, armrests,
and moveable straps to secure and support the child’s pelvis and trunk while also
allowing for as much independent movement as possible. Other features selected to
facilitate muscle activation by the child include a footrest to allow the use of leg muscles
in rocking and, a feature allowing for adjustment of the rocking motion to explore the
effects this has on patterns of muscle activation and sensory response.
Practical and aesthetic needs were largely concerned with making the chair easy
and enjoyable to use. To meet the need for the chair to fit the target population (age 1-12;
up to 59kg), the footrest was made adjustable, and two commercial rocking chair seats of

33
different sizes were modified to attach interchangeably to the base of the chair, and to
adjust forward and back. The need to appeal to children in the target population was met
partly by the inherent appeal of rocking, but also by painting the base of the chair with
attractive ocean scenes to stimulate the children’s imagination.
To meet the need to track the child’s use of the rocking chair, a position sensor,
which tracks the motion of the seat during rocking was added to the rocking chair to
make it possible to record the amplitude and duration of rocking. Force sensors were
also added to the footrest, seat, and armrests to detect the forces applied to the rocking
chair during rocking.
3.5.2 Final Prototype Design
The final prototype design incorporating the selected features was based on a
glider style rocker, which uses linkages to suspend the seat of the chair from a base which
remains stable on the floor. Figure 8 shows the solid model of the design which was used
for motion studies and finite element analysis. Motion study results from early designs
identified a tendency for the seat of the rocker to not return to center after rocking. This
was corrected by adjusting the length and position of the linkages, until further motion
study results showed it to consistently return to center.

34
Figure 8: Rendered solid model of rocking chair design
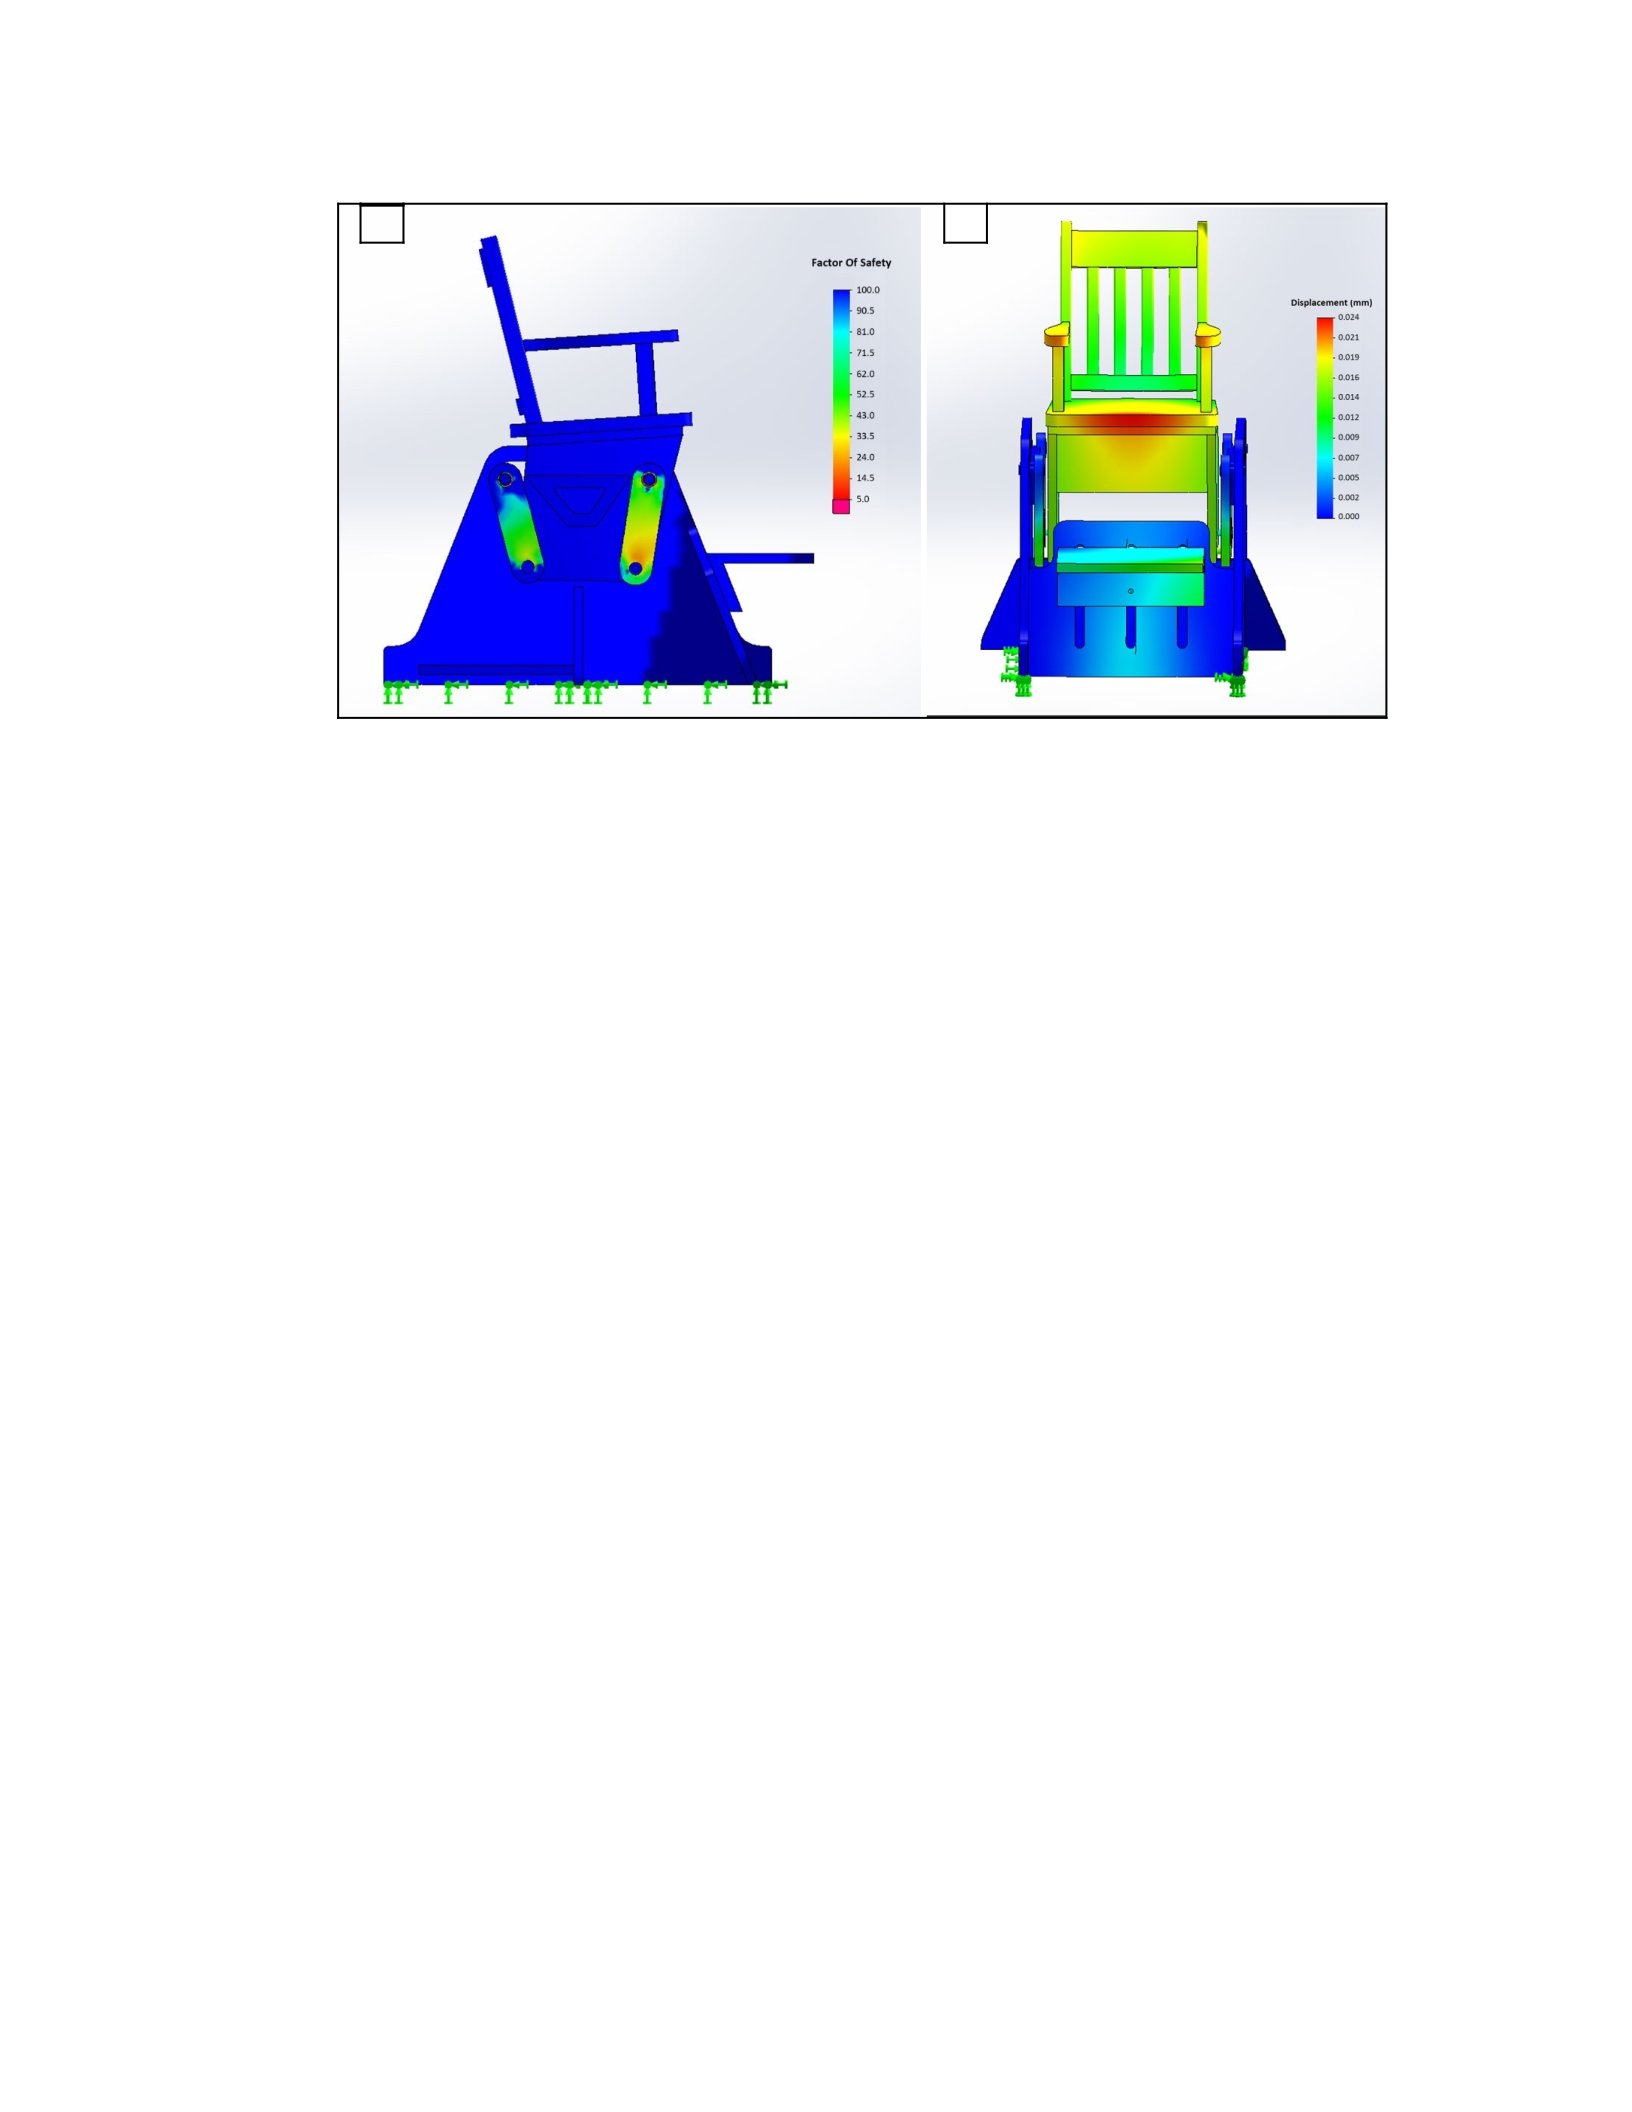
As shown in Figure 9, results from the finite element analysis of the final design
indicate that the minimum FOS, which occurs in the front linkage arms, is greater than 5
indicating that the chair is able to support at least five times the applied load of 136 kg
before failure. The maximum reported deflection is 0.024 mm.
35
AB
Figure 9: Finite Element Analysis results; A - Factor of Safety plot showing that
minimum FOS is >5; B – Deflection plot showing that maximum deflection is less
than .024 mm
3.5.3 Anthropometric Design Factors
Several design factors were directly related to the anthropometric characteristics
of the intended user population. The target specifications for each of these, and the actual
dimensions used in the final design are included in Table 4 along with design notes
about how the specifications were identified.
36
Table 4: Anthropometrics Driven Design Specifications
Design Targets vs. Actual
Dimensions Design notes
Small seat
max
depth
Design Target:
19 cm
Based on anthropometric data, to accommodate smallest children
without need for padding behind back.
Smaller seat should not be deeper than this.
Actual:
14 cm
Exact seat dimensions depend on the size of commercially available
children’s chairs that are compatible with chair base design.
Large
seat depth
Design Target:
36 cm
Target depth for large seat based upon buttock-popliteal length
data from the target population.
Actual:
38 cm
Exact seat dimensions depend on the size of commercially available
children’s chairs that are compatible with chair base design.
Footrest
to seat
range
Design Target:
23 – 40 cm
Based on anthropometric data (popliteal height) from target
population.
Actual:
22 – 34 cm
Larger range would require greater overall chair height,
which conflicts with need for chair stability.
3.5.4 Prototype Chair
Figure 10 shows selected rocking chair features, and stages in the build process as
well as the completed chair.
Selected materials for the chair build were as follows: Wooden parts were cut
from Baltic birch plywood and assembled using 10 x 3½ inch wood screws (Hillman
Deck*Plus) for all wood-to-wood connections. The seat portion of the chair was
suspended on four equal linkage arms (239mm x 64mm) with ½” ball bearings (R8ZZ
Shielded Bearings 1/2 x 1-1/8 x 5/16 Inch Ball Bearings) that were press fit into
appropriately sized cut-outs and captured with washers attached with wood screws as
shown in Figure 3D. The linkage arms were then attached to the base and chair with ½”-
13 bolts and hex nuts. A position sensor constructed of a rotary potentiometer (TT

37
AB
D
C
Figure 10: Rocking chair design details; Completed rocking chair (A); Painted base of
rocking chair(B); Detail of footrest adjustment locking mechanism (C); Detail of
bearing captured with washer in linkage arm, and revised safety stop (D).
Electronics, P160KNP) was installed on the base of the chair and coupled to one of the
chair’s linkage arms via spur gears. Two commercially available typical rocking chair
seats of different sizes (e.g., ECR4Kids Classic North American Oak Wood Rocking
Chair) were purchased and threaded studs (M6 x 50 mm) were added to the bottom of the
seat to enable attachment to the rocking chair base. Three vertical slots were cut in the
front of the chair base, with a ½”-13 bolt located in the middle slot to secure the footrest
in position. A plastic knob with threaded insert (Morton Glass Fiber Polyamide Multiple
Lobe Knob, Fluted Rim, Threaded Hole, ½”-13 Thread Size) was used to tighten the bolt

38
and secure the footrest in place. Wooden rails attach to the back of the footrest ramp in
the adjacent outside slots and serve to keep the footrest aligned correctly. Total cost for
all materials used and fabrication of parts on the ShopBot CNC router was kept under
US$ 400.
Safety Testing Results
3.6.1 Tipping Results
Tipping study results show that a minimum of 6.4 kg of force in the horizontal
direction at the top of the seat back is required for the chair to reach the tipping point.
This minimum force occurs at the lowest loading of 11 kg, and higher loads required
greater forces to tip. Overall, less force was required to tip the chair forward than to tip it
back or to the side. The force required to reach the tipping point at each load level for
each axis, as well as the lift height of the lifted side at the tipping point are shown in
Table 5.
Table 5: Chair tipping test results.
Chair loaded with 11, 35, or 59 kg (n=5 trials)
Mean tipping force (kg)
Mean lift height at tipping point (cm)
Tilt Direction 11 kg 35 kg 59 kg 11 kg 35 kg 59 kg
Forward 7.1 11.1 15.0 41.3 31.5 29.8
Back 9.1 14.7 17.4 42.5 33.6 28.8
Sideways 7.7 12.6 18.0 34.3 27.3 26.5
3.6.2 Maximum Load Results
While loaded, the chair was observed for stability, deflection of weight bearing
members, and structural integrity. No sign of weakness or instability was observed during

39
testing. After removing all weights from the chair seat, the assembly was inspected, and
no structural damage was observed.
3.6.3 Chair Strength and Stability Results (Dynamic Loading)
During dynamic testing, the original safety stop design was found to allow the
chair to bypass the rear stop and capsize at the 59kg (130 lbs) loading level. Based on this
result, the safety stop was redesigned, and the test was repeated with the new safety stop,
which performed well in all tests. No other signs of structural damage or weakness were
observed. At maximum rocking amplitudes, the chair tipped slightly on impact with the
safety stop at the maximum limit of travel. Comparing the angle of tilt during dynamic
rocking to the tipping point angle during tipping tests, the maximum angle of tilt during
dynamic testing was less than 1/3 of the tipping point angle that would be required to
cause the chair to overturn. This adds confidence that the chair will remain stable during
normal rocking. The full array of tilt angles observed during dynamic testing and their
relation to the tipping point are included in Table 5.
Table 6: Chair tilt angle during dynamic loading.
Load Tilt Direction Mean
dynamic tilt*
(degrees)
Maximum
dynamic tilt
(degrees)
Mean tipping
point†
(degrees)
Tipping point
safety factorŧ
11 kg Forward 5.3 6.4 33.4 5.3
Backward 2.1 2.8 34.6 12.2
35 kg Forward 5.5 6.9 24.8 3.6
Backward 4.6 5.0 26.6 5.3
59 kg Forward 5.5 6.7 29.8 4.4
Backward 3.3 3.7 22.6 6.1
*n=10; †n=5; ŧ Tipping point safety factor represents the ratio of tipping angle to maximum dynamic tilt
angle at a given load level.

40
Discussion
This project aimed to apply engineering design methodologies to develop a
rocking chair specifically for children with spinal cord injury (SCI) to promote trunk
control. Throughout the process, the needs identified in the QFD design process
were used to guide design choices, and to evaluate the final design.
Safety was the highest rated need category and was one of the primary reasons for
designing a custom rocking chair rather than simply adapting a commercially available
rocker. The choice of a glider type rocker, rather than a more traditional rocking chair,
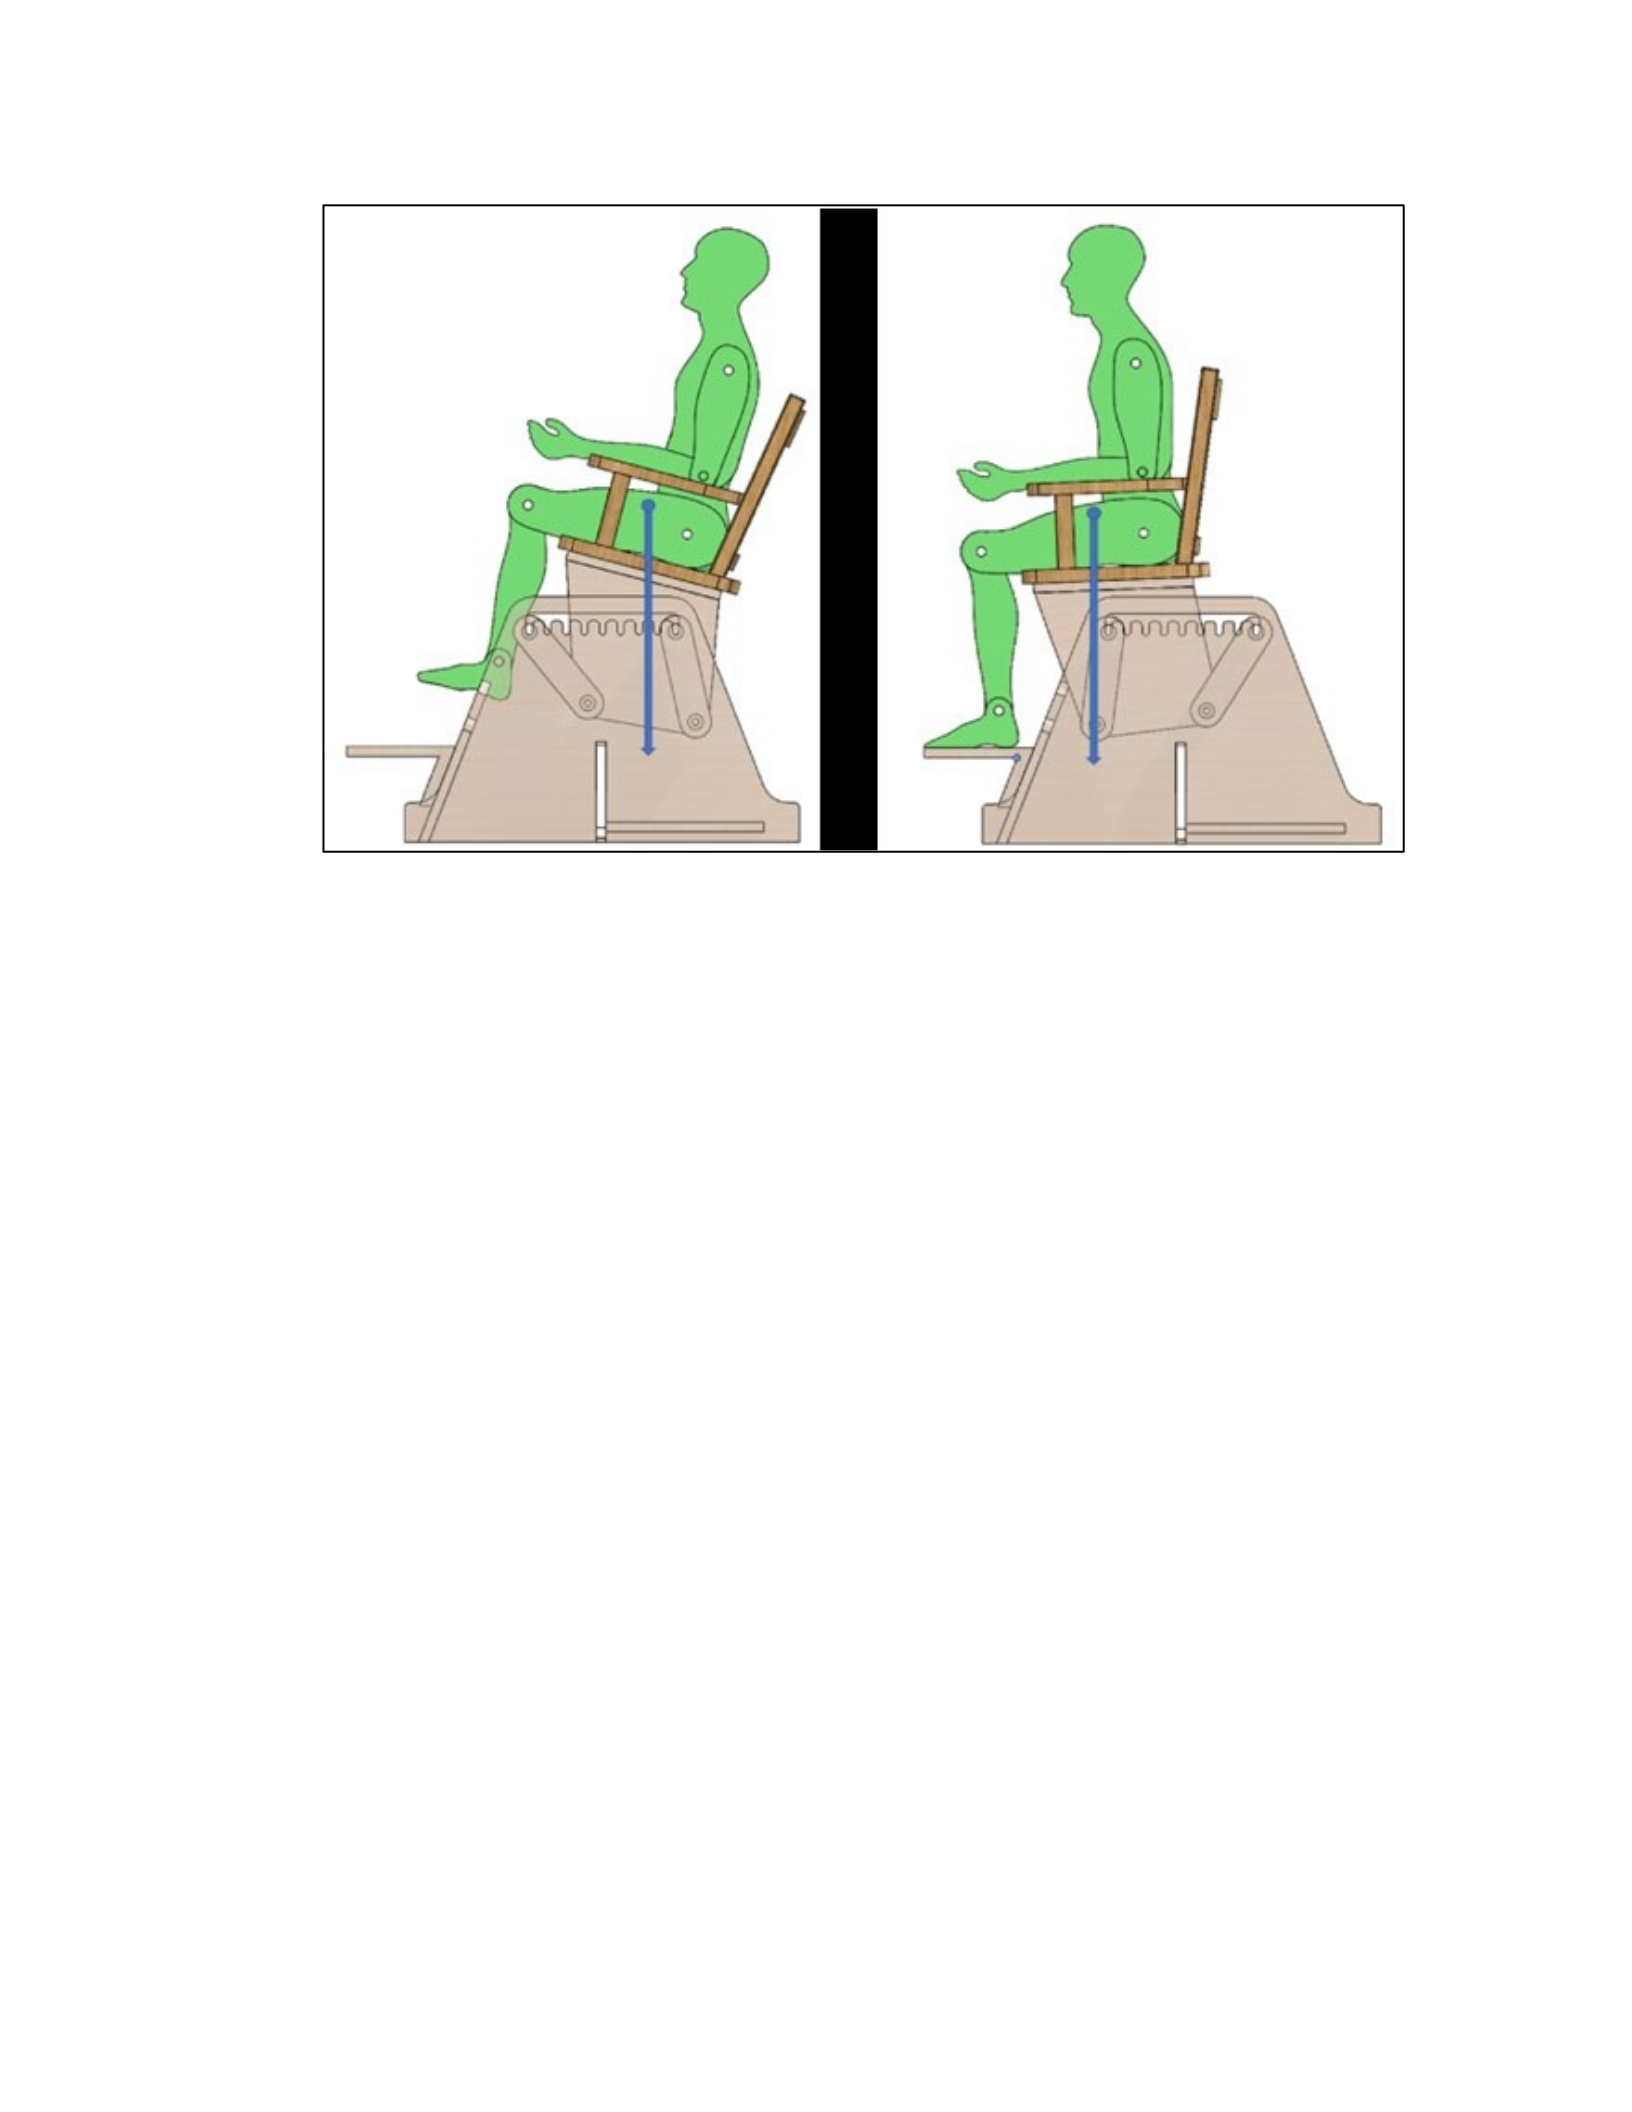
was made primarily to provide a stable base which would resist tip-over. As shown in
Figure 11, it is possible to limit the possible range of motion of this type of chair so that
the center of gravity cannot move outside of the footprint of the base. This makes the
chair naturally resistant to tipping.
Further evidence that the chair will resist tipping was provided by the results of
physical testing which showed that at maximum amplitude of rocking under various
loads, the chair does not come close to the tipping point. As seen in Table 5, the
minimum tipping point factor of safety, defined as the ratio of the tipping point angle to
the maximum dynamic tilt angle, is 3.6. This indicates that the chair would have to tip at
an angle more than three times greater than what is actually seen in dynamic testing
before tipping over. Other physical testing showed that the chair was capable of
supporting the desired loads with an ample factor of safety.
The glider type rocker also has advantages with respect to meeting therapeutic
needs. Independent movement, sensory stimulation, and muscle activation in arms, legs
41
Figure 11: Rocking chair center of mass At maximum forward and back rocking,
center of mass (blue arrow) stays within footprint of rocking chair and no overturning
moment is created.
and trunk are all identified needs. The large, stable base of the glider type rocker provides
a place to mount a footrest. Patients who have some leg control will be able to use the
footrest to move the chair, providing a way to activate leg muscles. For patients without
leg control, foot placement on the footrest will allow legs to flex as the chair rocks,
stimulating sensory input to the spinal cord from the legs and feet.
Several of the features contributed towards meeting multiple needs. For instance,
in addition to helping meet therapeutic needs, the footrest was also made adjustable to
help meet the need for the chair fit children in the target population. Similarly, straps that
could be adjusted higher and lower on the child’s trunk helped to meet needs for safety,
while also allowing as much independent trunk movement as possible.
42
The prototype rocking chair is intended for use in further studies in children with
SCI to characterize muscle activation during rocking. As such, some features intended
primarily for convenience in home use were not implemented in the current build but will
likely be implemented in future version of the chair. These include features such as a
mechanism to prevent the chair from rocking during transfers, wheels and handles to aid
in transport, and a detachable work surface for use during other activities.
Limitations
There are several limitations to this work. Lack of human testing in the target
population limits the ability to validate that the design meets the defined needs when
used by children with SCI. Also, until human testing has been completed it will be
unclear what clinical relevance rocking has for these children.
Future Work
Plans for future work include studies with children with SCI to validate that the
chair meets the identified needs when used by the target population. One need in
particular which could not be evaluated without having children rock in the rocking chair
was the need for an activity that is enjoyable for children with SCI. This need was
emphasized by therapists as one of the most important for children in this age group since
enjoyment of an activity leads to motivation to engage in that activity, additional time
spent in the activity, and better results from the activity. Additionally, efforts will be
made to characterize muscle activation patterns in arms, legs and trunk during rocking to
determine if rocking is an effective means of stimulating activation in muscles involved
with trunk control.

43
Conclusion
This prototype rocking chair provides an opportunity to safely study rocking as a
means of improving trunk control in children with spinal cord injuries. Further testing
and refinement of the design, as well as the incorporation of embedded sensors to
provide feedback on how the chair is used all hold potential for extending its usefulness.
Ultimately, rocking may evolve into a valuable tool for therapists seeking a safe,
accessible means for children with SCI and impaired trunk muscles to safely rock and
activate their trunk muscles.

44
CHAPTER 4
MUSCLE ACTIVATION DURING ROCKING
4.1 Introduction
Spinal cord injury (SCI) is a debilitating condition that significantly impacts
quality of life. Children with SCI in particular face numerous physical, emotional, and
psychological challenges that often impede their overall development and well-being
[25]. SCI is known to cause long term complications including negative effects on
respiration, bladder and bowel control, cardiovascular function and head/trunk control
[11]. Moreover, SCI in children is more likely to result in secondary conditions, such as
scoliosis, respiratory complications, hip dysplasia, and pressure ulcers [11, 28], and the
incidence of these conditions is greater for children injured at younger ages [3, 17, 27,
28].
4.1.1 Activity Based Therapy
With the existing state of the art science currently unable to fully resolve or
ameliorate the various types and severities of paralysis associated with SCI, traditional
rehabilitation approaches focus on compensation for paralysis via assistive devices,
behavioral strategies, and adaptations to the environment to achieve mobility and
function, and to facilitate activities of daily living [58]. However, researchers have
recently demonstrated that activity-based therapy (ABT) is an effective intervention for
at least partial restoration of intrinsic trunk control, as measured by SATCo score, in
children with SCI [33]. The purpose of ABT is to activate the neuromuscular system

45
below the level of injury, and to promote the restoration of neuromuscular capacity. ABT
interventions include locomotor training (facilitated walking on a treadmill) with partial
body weight support (systems that modulate the offset of patient weight during the gait
cycle), which aims to mimic typical standing/walking patterns, reinforce appropriate
alignment of the trunk, pelvis, and lower extremities providing locomotor-specific
sensorimotor input to the neural axis [19, 39]. In addition to training on the treadmill, off-
treadmill interventions utilize the activated neuromuscular system targeting task-specific
motor activities to integrate use of the progressively activated trunk in typical activities
such as reaching, standing, and sit-to-stand [33]. ABT also focuses on home and
community integration by giving children opportunities to utilize their new capacity and
practice in a variety of everyday and functional activities [36].
Community integration considerations create opportunities to develop additional
reinforcing activities that increase practice with new neuromuscular capacities and can be
performed in the home and community. From that perspective, rocking in a rocking chair
was explored in a case report by Argetsinger et al [40]. This study describes the trial of a
pediatric rocking chair adapted for use by a child with SCI as an activity intended to
support gains in trunk postural control outside of the clinic. Rocking in this chair created
a self-initiated activity that promoted an upright posture and engaged trunk and arm
muscles with little to no assistance by caregivers. Validating the effectiveness of this
approach in applying the gains acquired through locomotor training is a critical next step
to inform clinical decision-making.

46
4.1.2 Study Rationale
To better understand the effectiveness of rocking in the context of pediatric SCI,
this study aims to answer the following research questions: 1) Does rocking in a rocking
chair activate trunk muscles in children with SCI and in typically developing (TD)
children? 2) What are typical temporal muscle activation patterns during a rocking cycle
in children with SCI, and how do these patterns differ from those seen in TD children? 3)
Is there a correlation between intrinsic trunk control, as measured by SATCo, and trunk
muscle activation during rocking?
In addition to these specific technical questions, it is important to investigate
practical factors that impact the rocking experience of the user. These factors include the
child’s enjoyment of rocking, and the safety and functionality of the rocking chair
prototype.
4.2 Materials and Methods
A thorough examination of the concept, design methodology, fabrication, and
safety testing of the rocking chair have been described previously [59]. Briefly, to
develop new technology for accomplishing the goals of this study, a custom rocking chair
specifically designed for children with spinal cord injuries was fabricated. Based on a
glider style rocking chair to ensure stability and safety, the base of the chair was
assembled from parts fabricated using Baltic birch plywood, a well-known furniture
material which provided both durability and cost benefits and promoted ease of chair
assembly. Seats from commercially available pediatric-scale rocking chairs of two
different sizes were adapted to attach interchangeably to the custom base to
accommodate children of varying sizes. An adjustable height footrest was also included

47
in the design of the rocking chair

48
base to accommodate taller children.
To quantify the amplitude of rocking and to enable tracking of the temporal
location of muscle activation in the rocking cycle, a custom chair angle/tilt sensor was
incorporated into the design. This included a shafted potentiometer configured so that
the rotational position of the shaft was adjusted by the angular movement of one of the
chair suspension arm bearings during the rocking motion. This sensor generated a
dynamic voltage which, when converted to angle of rotation, accurately reported the
position of the seat as it was dynamically rotated from its neutral position by the user.
4.2.1 Participant Recruitment
The current study was performed under an Institutional Review Board (IRB)
approved protocol for parental/caregiver informed consent and assent for children older
than 7 years (University of Louisville IRB #17.0725). Two cohorts were enrolled:
children with SCI and TD children, based on specific eligibility criteria. Children with
SCI, age 1-12 years and currently participating in locomotor training, recently discharged
(< 1 month) or, if discharged between 1 and 24 months prior, were eligible with a
medical screening to determine health status and/or safety concerns. For TD children, age
1-12 years with no history of SCI or presence of neurological disorder, musculoskeletal
disease, cardiovascular, pulmonary, or respiratory condition that would affect typical
function, and the ability to follow age-appropriate instructions were eligible. For both
cohorts, children with a physical condition or recent illness, identified via medical screen,
that would prevent participation in rocking were excluded.

49
4.2.2 Participant Characteristics
A total of 11 children with SCI and 10 TD children were enrolled over a 22-
month period. Age and height at time of testing, and sex were recorded for all
participants in both groups. American Spinal Injury Association (ASIA) Impairment
Scale (AIS) [60] was recorded for participants in the SCI group whose age and etiology
allowed it to be determined. Injury level, time since injury, etiology, and SATCo scores
were also recorded for participants in the SCI group. SATCo score is an indication of a
child’s capacity to sit upright in both static and dynamic conditions with a facilitated
neutral pelvis position and varying biomechanical levels of trunk support, and represents
the patient’s inherent, uncompensated level of trunk control [33]. Scores range from 0 to
20, with higher values indicating better trunk control. SATCo was the primary measure
of trunk control impairment and a primary descriptor of the population with SCI
participating in this study.
4.2.3 Anthropometrics and Rocking Chair Fit
When considering the design and setup of the rocking chair, it was important to
take the anthropometric characteristics of the users into consideration. The following
anatomical features were considered to be important anthropometric measurements that
might affect rocking chair fit.
Popliteal Height (PH) is the measurement from bottom of foot to underside of
thigh while sitting. This helps to determine footrest height relative to the top of the seat.
For a stationary chair, the seat to floor distance could match the PH, but for a rocking
chair this leads to the feet lifting off the footrest as the chair rocks back. Consequently,

50
the footrest should be set up so that, the knees are slightly elevated off the seat when the
chair is centered in the neutral position, and the feet do not lift when the chair rocks back.
Buttock-popliteal length (PBL) is the measurement from behind the buttock to the
back of the lower leg just below the knee while sitting. This determines the depth of the
seat measured from the front edge of the seat to the backrest of the chair (or to padding
placed behind the user’s back). The seat depth should be less than the BPL to allow for
movement of legs during rocking. If the seat is too deep, padding can be added behind
the child, but too much padding may disrupt the balance of the chair by moving the user’s
center of gravity forward.
User weight can interact with seat adjustments that move the center of balance
forward or back due to size factors, such as when a smaller child has padding placed
behind their back, or a larger child has the seat moved back. This is primarily a problem
for larger, heavier children since a smaller child’s weight is usually not enough to change
the balance significantly.
Trunk width does not affect chair motion but should be checked to ensure that the
child can sit comfortably with no squeezing or chafing from the sides of the chair.
4.2.4 Rocking Chair Setup and Fit Adjustment
Table 7 is a table of identified parameters that were considered when seating a
child in the chair, including methods of adjustment for optimal fit and balance. When
setting up the chair, it may be impossible to meet all the fit criteria simultaneously. For
instance, if the seat balance is too far back, and the footrest has already been adjusted all
the way down, it may not be possible to move the child forward to correct the balance
without moving them too close to the footrest.

51
Table 7: Chair Setup and Fitting Parameters
Fitting
parameter Definition and adjustment
Seated
balance
When sitting still in the rocking chair, the seat should not tilt more than 10 degrees in
either direction from the neutral position. This can be compensated for by adding padding
behind the child to move them forward, or by sliding the seat back or forward, or by
switching to the larger/smaller seat.
Footrest
placement
When the child rocks back in the rocking chair, the feet should not lift off footrest. This
means that in the neutral position, there will be a gap between the front edge of the top of
the seat and bottom of the child’s leg just above the knee. The size of the gap will vary
depending on the chair setup and child size, so the most reliable way to check this is to
watch the child rock and adjust the footrest position until the bottoms of the legs (behind
the knee) just touch the top of the seat when the chair reaches its farthest-back position,
and the feet do not lift off the footrest.
Seat depth When the child rocks all the way forward, the backs of the calves should not bump the
front of the seat. If they do, switch to the smaller seat, or add padding behind the user to
decrease the effective seat depth.
Seat width When seating the child, the width of the chair should be checked to ensure that it is not
too tight. If the sides of the seat squeeze or rub against the child significantly, the larger
seat should be used if possible. Other width adjustments are not possible with the current
design
Child
weight
The chair has been tested and is safe for up to 130 lbs. Children heavier than this should
not use the chair.
4.2.5 Chair Functionality Assessment
To validate the basic operation of the chair, a TD child first evaluated the chair by
sitting in the seat to test its balance, followed by rocking to assess both comfort and
function. Once basic chair operation was verified, children with SCI were allowed to rock
in the chair. Children were asked to rock in several different ways to evaluate which
muscles they were capable of using to rock the chair: 1) Free rocking, allowing
participants to rock in any manner of their choosing; 2) arms-off-armrests, to promote use
of trunk muscles; 3) leg-only rocking, restricting trunk motion to assess the contribution
of leg muscles to rocking; 4) footrest removed, so that only upper body muscles
contribute to rocking. Results from these modes of rocking were noted and compiled to
better understand muscle use strategies.

52
During rocking sessions, children were observed closely while technicians
engaged with them in conversation to understand their experience. Enjoyment of rocking,
difficulties with making the chair rock, methods of initiating and maintaining rocking,
and any potential safety or practical issues were observed and noted. Additionally,
parents, children, engineers, and therapists engaged in debriefing conversations after
each rocking session to obtain reactions and feedback, and to suggest possible
improvements to the chair and protocols. Videos of rocking sessions were also reviewed
to ensure that all data pertaining to chair use had been captured.
4.2.6 Surface Electromyography (sEMG) Data Acquisition
sEMG signals from muscles in the arms, legs, and trunk of both TD and SCI
groups were recorded using wireless electrodes (Cometa Pico EMG, , pre-amplified,
bipolar , 29 mm electrode spacing, 2000 Hz sampling rate, Cometa SRL, Milan, IT) as
shown in Table 6.
Table 8: Muscles targeted for EMG readings
Trunk Muscles Arm Leg
Cervical paraspinal (PSC) Biceps brachii (BB) Rectus femoris (RF)
Thoracic paraspinal (PST) Long head of triceps (TB) Medial hamstring (MH)
Lumbar paraspinal (PSL) Pectoralis (PEC) Tibialis anterior (TA)
Rectus abdominis (RA) Medial gastrocnemius (MG)
Oblique (OB)
Appropriate locations on the skin above the muscle of interest were prepared by
cleaning with alcohol swabs, then electrodes were placed over each muscle while the
child was seated on a stationary table (see appendix D for full electrode placement
protocol). Subjects were then asked to sit in (TD) or were placed in (SCI) the chair
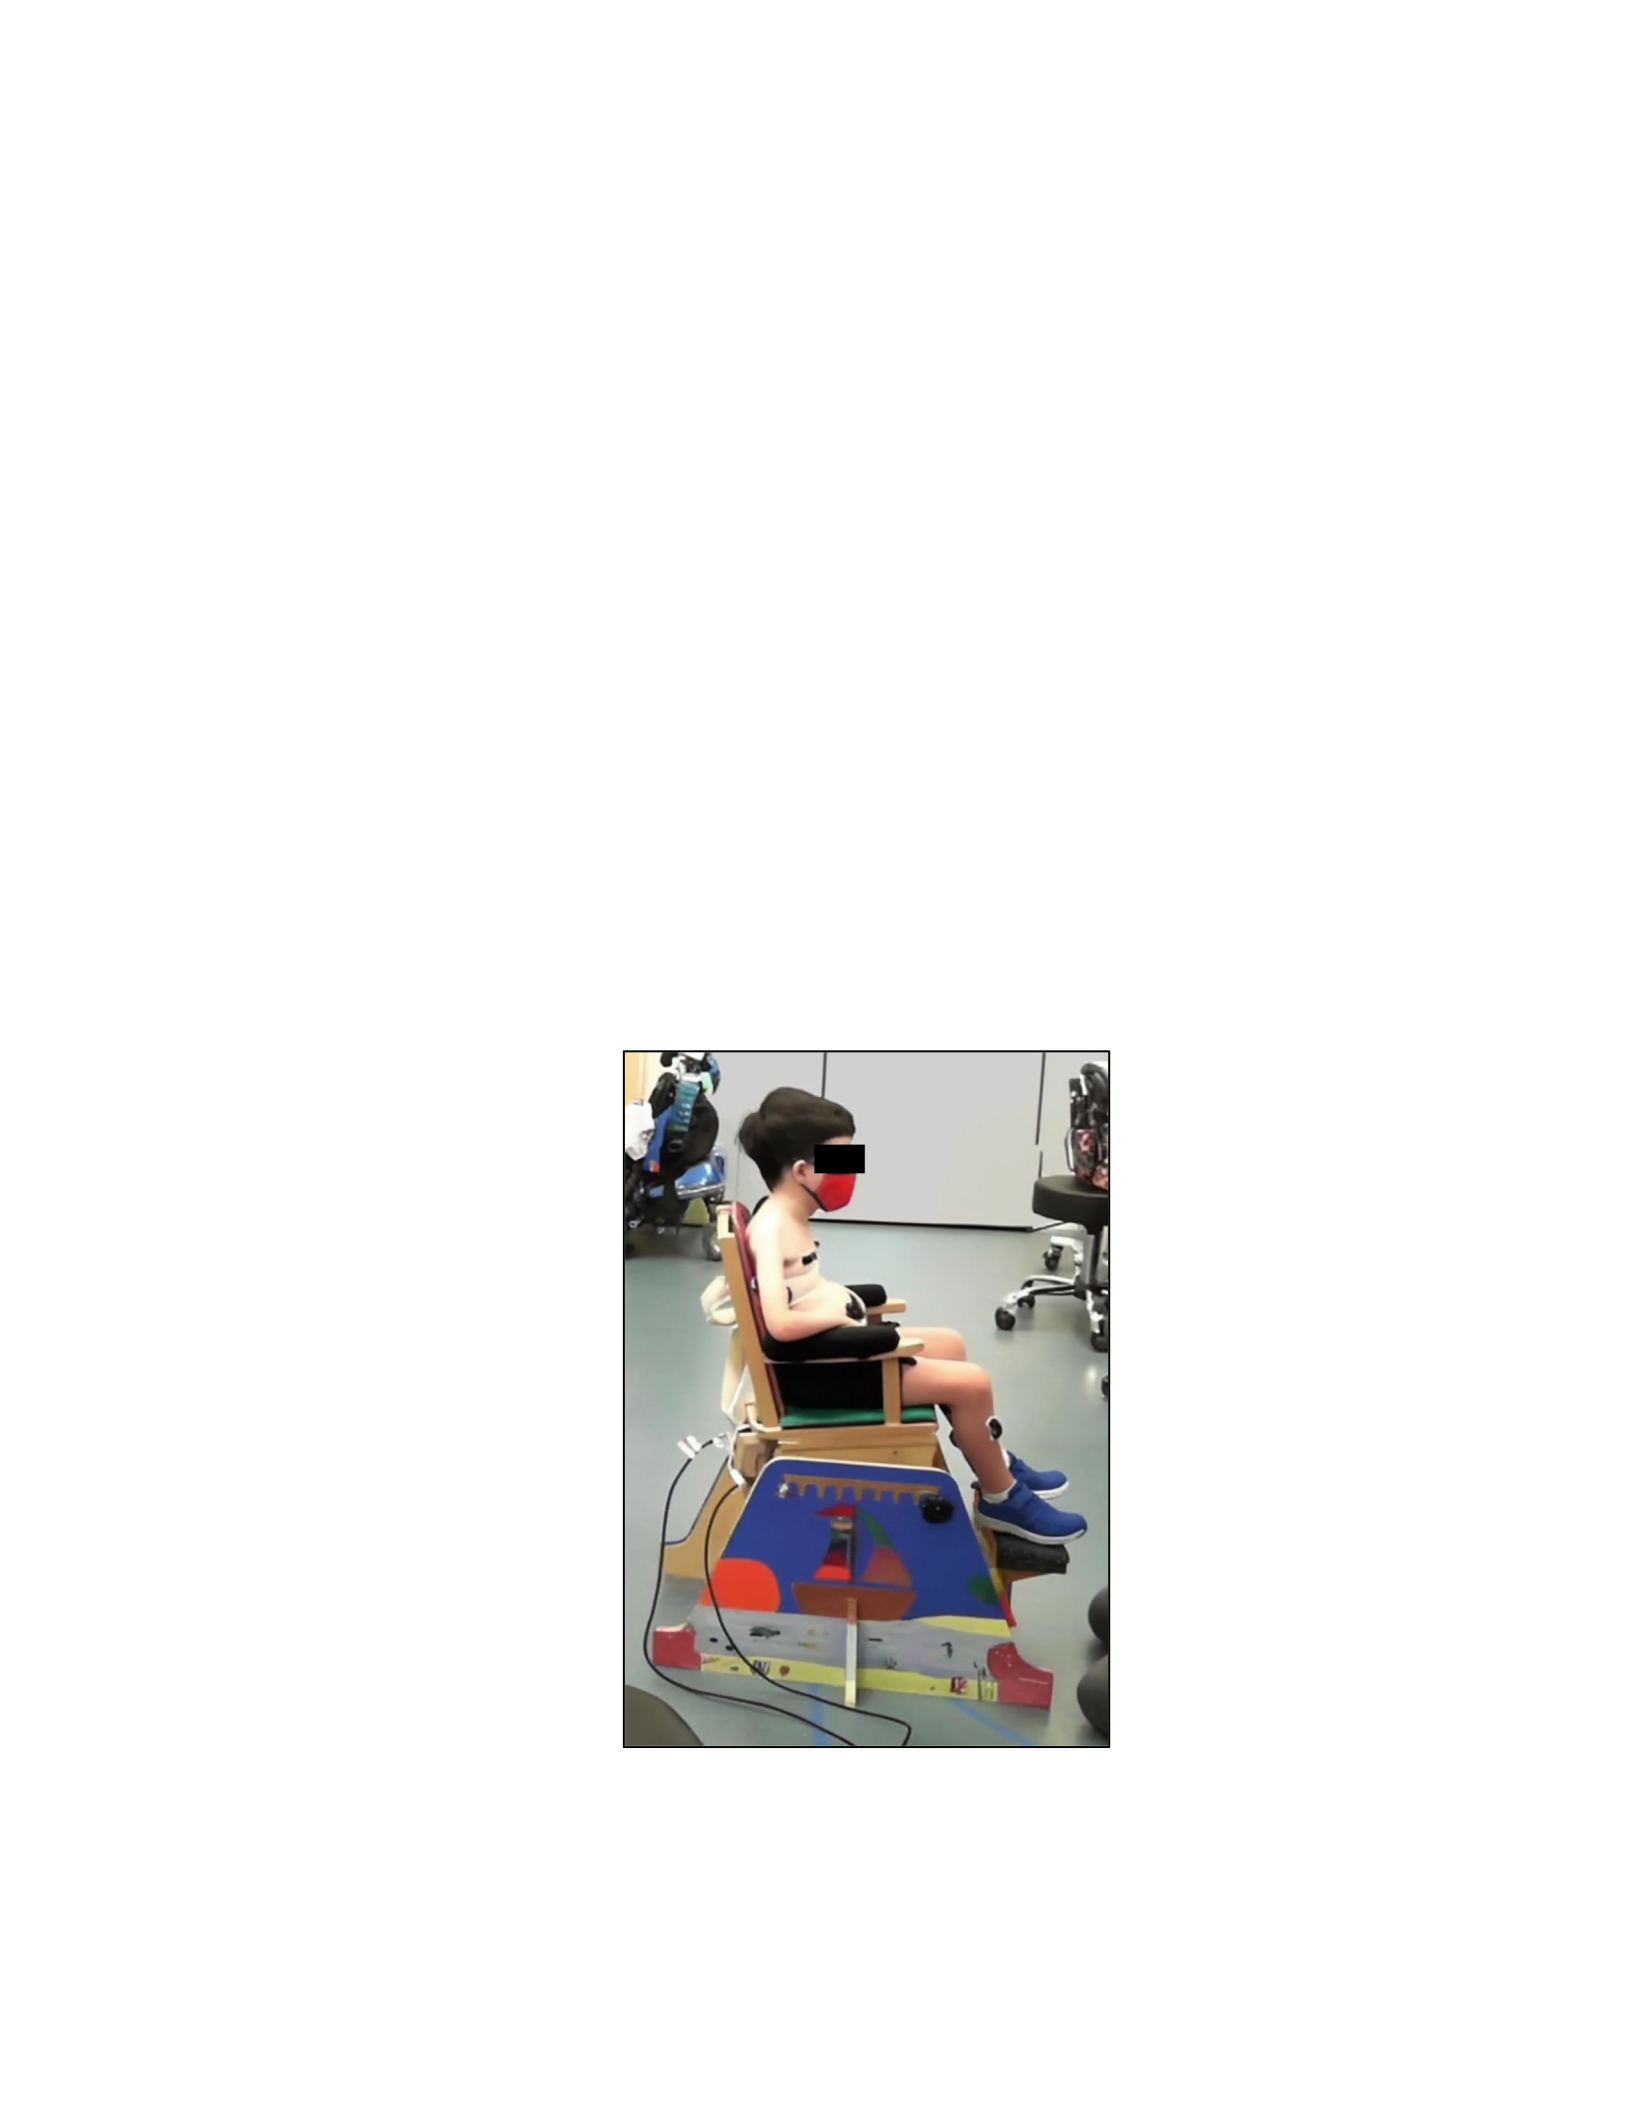
53
(example in Figure 12), a safety strap was placed around the waist, and additional straps
placed higher on the trunk if necessary for support.
Each child was instructed to sit quietly for one minute while sEMG was recorded
to establish baseline muscle activation. All children were then instructed to rock in the
chair using whatever methods were most natural to them. Once the child was accustomed
to rocking and was observed to be rocking in a regular rhythm, sEMG was recorded for
one minute. This process was repeated for the other three modes of rocking. Appendix D
includes an outline of the full data collection protocol.
sEMG data was acquired at 2000 Hz and imported into MATLAB. sEMG data
offset was removed by subtracting the mean value of all data points from each data point,
Figure 12: A participant with SCI using the custom rocking chair prototype.Note: strap
around chest for support, and footrest raised to support feet.
54
and a 300-point moving window root mean square (RMS) was calculated for all datasets
using custom MATLAB scripts (Appendix A).
4.2.7 Rocking Cycle
For this study, a single rocking cycle was defined as the position of the chair as it
swings from the extreme front position to the extreme rear position and back to the front.
Thus, the beginning and end of the cycle is defined as the point at which the chair
reverses direction at the front of the cycle. As shown in Figure 13, the cycle was broken
into two phases: Phase 1 is backward (BW) motion, starting with the chair all the way
forward, and lasting while the chair swings backward to the farthest back point in the
Figure 13: Sample position sensor data from one rocking cycle, to highlight cyclical
phase of rocking Center vertical line marks change in direction; left quadrant is
backward motion; right quadrant is forward motion.

55
cycle. Phase 2 is forward (FW) motion, starting with the chair at the farthest back point,
and lasting until the end of the cycle with the chair again at the farthest forward point.
Each of these phases was divided into early (EBW, EFW) and late (LBW, LFW) stages.
Accordingly, the chair rocking direction reverses from forward to backward at the end
point of the cycle, and reverses from backward to forward at the midpoint of the cycle.
4.2.8 Artifact Removal in sEMG Data
As is common with sEMG data, many of the trunk muscle data sets were
contaminated with cardiac artifacts. To remove this interference, two methods were used.
For data used to calculate increase in muscle activation while rocking, it was possible to
use the data between heartbeats to calculate the magnitude of the sEMG signal. To delete
the contaminated data, a custom MATLAB script (Appendix A) was used to identify the
interfering signals and delete them from the dataset. Before running this script, each
dataset was manually inspected to determine an appropriate threshold for detecting
heartbeats. Typically, the cardiac signal was strongest in the left pectoral sEMG, so this
signal was used initially to locate the heartbeats, and the start and end points of each
heartbeat were identified. The erroneous data was then deleted from all data streams and
the remaining data was concatenated.
To determine the temporal patterns of muscle activation during the rocking
cycle, it was necessary to use a method of cardiac contamination removal that preserved
the time-dependent nature of the data. Similar to the previous method, this involved
identification of the start and end of each heartbeat. Since there was both significant
variation in the strength of the cardiac signal across full session recordings and variation
between subjects regarding which muscle activation data was contaminated, the data

56
from each trunk muscle was manually inspected. Muscle activity recordings with
contamination were flagged for correction, and the contaminated data was deleted. A
custom MATLAB script (Appendix A) was written to detect the rocking cycles, and
missing data that had been deleted due to cardiac contamination was replaced by the
averaged data from the same point in the rocking cycles with intact data for that part of
the cycle.
In addition to the cardiac contamination, there were also two other, less prevalent,
sources of data contamination. First, to capture data from the desired muscles, some
sEMG sensor bodies were required to be positioned in locations that brought them into
contact with the seat during rocking, potentially introducing artifacts into the recorded
data in the event of a collision. Second, extraneous movements on the part of the child,
such as a hand gesture, could introduce a signal unrelated to the rocking cycle into the
data. These were identified and removed manually by inspecting the EMG data and
cross-referencing with the corresponding video recording of the data collection session.
4.2.9 Muscle Activation Amplitude Calculation
For each participant, the mean sEMG (RMS) amplitude during rocking was
calculated for each muscle. Baseline amplitude was also calculated by taking the three
second period with the lowest mean sEMG (RMS) amplitude during quiet sitting for each
muscle. Normalized activation amplitude for each muscle was calculated by subtracting
the baseline amplitude from the mean amplitude during rocking of the corresponding
muscle. Normalized activations were then plotted in a heatmap.

57
4.2.10 Prototype Cycle Creation
To determine the timing of muscle activation within the rocking cycle, an average
or “prototype” rocking cycle was created for each muscle. To do this, a custom
MATLAB script (Appendix A) was used to break the EMG data from each subject into
rocking cycles using the data from the position sensor mounted on the rocking chair.
These activation cycles for each muscle were averaged for each subject, and the resulting
average cycles were normalized to a scale of 0 to 1 using the formula:
𝑃
𝑛
− 𝐶𝑦𝑐𝑙𝑒
𝑚𝑖𝑛
𝐶𝑦𝑐𝑙𝑒
𝑚𝑎𝑥
−
𝐶𝑦𝑐𝑙𝑒
𝑚𝑖𝑛
Eq. 1
where Pn is the nth data point, Cyclemax is the maximum value for the given muscle, and
Cyclemin is the minimum value for the given muscle. The normalized cycles for each
muscle were then averaged for the SCI group and the TD group, to produce typical
activation cycles, and the resulting curves were again normalized to a scale of 0 to 1.
The normalized cycles for each muscle were plotted with SCI and TD data on the
same graph to facilitate comparison.
4.2.11 Statistics
To address the first research question, “does rocking in a rocking chair activate
trunk muscles in children with SCI and in TD children?” the mean sEMG (RMS)
amplitude during rocking was calculated for each muscle activity recorded. Baseline
amplitude was also calculated by taking the three second period with the lowest mean
sEMG (RMS) amplitude during quiet sitting for each muscle. One-sided signed-rank tests
were then used to test the hypothesis that for both SCI and TD groups, sEMG amplitude
(RMS) for each muscle during rocking would be greater than baseline sEMG amplitude

58
(RMS) for the same muscle during quiet sitting. P-values were corrected for multiple
hypothesis testing using the Holm-Sidak method [61].
To address the second research question, ”What are typical temporal muscle
activation patterns during a rocking cycle in children with SCI, and how do these patterns
differ from those seen in TD children?” cluster analysis was used to investigate how the
timing of muscle activation in the SCI group compared to those observed in the TD
group, and to determine if different rocking styles contributed to different muscle
activation patterns in trunk muscles. To achieve this, the rocking cycle was subdivided
into four segments, as described previously, and shown in Figure 13. EBW (first 25% of
the cycle), LBW (26-50%), EFW (51-75%), and LFW (76-100%). A custom MATLAB
script (Appendix A) was used to calculate the mean normalized muscle activation within
these segments for each subject and each trunk muscle. This data was aggregated and
used to perform cluster analysis. Cluster analysis was performed in MATLAB, using the
‘linkage’ function with the ‘average’ distance method to find clusters of subjects who
used similar temporal muscle activation patterns while rocking. After clusters were
identified, distance between each SCI subject and the TD cluster was calculated using the
formula:
𝐷 = (𝑇𝐷�25 − 𝑆𝐶𝐼25)2 + (𝑇𝐷50 − 𝑆𝐶𝐼50)2+(𝑇𝐷75 − 𝑆𝐶𝐼75)2 +
(𝑇𝐷100 − 𝑆𝐶𝐼100)2Eq. 2
where D equals distance, and TDx and SCIx represent the mean activation for the given
muscle over the respective segment of the rocking cycle. These distances were then used
to determine which SCI clusters were more similar to the TD cluster, and the mean
activations were plotted for the TD subjects and each SCI cluster [62].

59
Two-sided t-tests were used to test for differences in activation in each segment
between the TD group and each of the SCI clusters, and significant differences were
noted on plots.
To examine the third research question, “Is there a correlation between intrinsic
trunk control, as measured by SATCo, and trunk muscle activation during rocking?”
Spearman correlation analysis was performed to assess the correlation between SATCo
scores and trunk muscle activation amplitude. For purposes of this analysis the two
children with acute flaccid myelitis (AFM) were excluded as their impairment
presentations are atypical, not uniform across spinal cord levels, and often reflect greater
to lesser impairment in a cephalad-caudal direction. In contrast, other participants
demonstrate higher SATCo scores with greater control and activation of lower thoraco-
lumbar muscles. Results were compiled in a table and significant correlations were noted.
All confidence levels were set at 95% (p < 0.05). Prism 10 (GraphPad Software,
San Diego, CA, USA) was used for the analysis.
4.3 Results
4.3.1 Participant Characteristics
Characteristics of participants including age, height, SATCO score, and injury
related details are shown in Table 9.
The SCI group included 7 males and 4 females between 3 and 11 years of age
(mean = 7.1, SD = 2.7), and heights ranging from 77 to 42 cm (mean = 120, SD = 22).
SATCo scores ranged from 0 to 19 (out of 20) (mean = 13.1, SD = 5.8). Two children
presented with cervical SCI, 6 with thoracic SCI, and 1 with lumbar SCI. Time since
injury ranged from 1.5 to 6.5 years (mean = 4.1, SD = 1.7).

60
The TD group included 6 males and 4 females with ages ranging from 5 to 11
years (mean = 7.2, SD = 2.4), and heights from 111 to 143 cm (mean = 128, SD = 14).
Table 9: Participant characteristics
Participant
ID
Group Age
(yrs)
Sex Height
(cm)
SATCo
Score
AIS Injury
level
Time since
injury (yrs)
MOI Etiology
P216 SCI 7 M 131 0 * - 1.5 NT Acute Flaccid Myelitis
P188 SCI 4 F 94 8 * T2-T5 4 NT Myelomalacia
P23 SCI 7 M 140 11 B C4-C7 4.5 NT Transverse Myelitis
P34 SCI 8 M 128 11 A T2-T8 6.5 NT Spinal Astrocytoma
P32 SCI 9 F 129 12 A T2-T3 6 T Motor Vehicle Accident
P187 SCI 3 M 77 12 * T11 2.5 NT Spinal Cord Ischemia
P204 SCI 9 M 130 15 A L4 2 T Motor Vehicle Accident
P217 SCI 3 M 91 18 * C1-C3 3 NT Perinatal
P15 SCI 9 F 127 19 A T12 5.5 NT Epidural Abscess
P21 SCI 11 F 142 19 A T10 5 NT Spinal Stroke
P215 SCI 9 M 139 19 * - 4 NT Acute Flaccid Myelitis
SCI Mean (SD) 7.1 (2.7) 120 (22) 13.1 (5.8) 4.1 (1.7)
SCI Median (IQR) 7.8
(5.5,9.0)
129
(110,135)
12.0
(11.0,18.5)
4.1 (2.8,5.2)
SCI Range 3-11 77-142 0-19 2-7
P218 TD 9 M 143 - - - -
P38 TD 8 F 129 - - - -
P219 TD 5 F - - - - -
P220 TD 5 M 115 - - - -
P221 TD 8 M 134 - - - -
P222 TD 5 F 111 - - - -
P223 TD 11 M 149 - - - -
P224 TD 9 M 141 - - - -
P225 TD 5 M 119 - - - -
P226 TD 5 F 113 - - - -
TD Mean (SD) 7.2 (2.4) 128 (14)
TD Median
(IQR)
6.5
(5.2,9.0)
129
(115,141)
TD Range 5-12 111-150
*AIS not valid under 5 years of age [63]; SCI = Spinal cord injury; TD = Typically Developing; SATCo = Segmental Assessment
of Trunk Control; AIS = ASIA Impairment Scale score; MOI = Mechanism of injury; T = traumatic; NT = Non-traumatic
4.3.2 Safety, Functionality, and Enjoyment
Data gathered during the observation of rocking sessions are summarized in Table
10.
Fit: Three of the children in the SCI group had minor issues with fit that were
addressed satisfactorily by adding padding to the footrest or behind their back. Two other
children had fit issues that couldn't be fully corrected. One was too big for the chair and

61
the balance was off towards the rear (participant P21 in Table 10 for details of chair
adjustments). The other was too small for the chair even with padding on both the
footrest and back of the seat (participant P187 in Table 10). Both these children were
still able to rock, but their rocking mechanics (how they rock, and their overall
experience rocking the chair) may have been affected by the balance and fit of the chair.
Safety: No adverse safety events or injuries were experienced during trials with
children in the rocking chair. It was however, observed that a cross brace under the
seat could create a potential pinch-point for smaller children.
Functionality: Regardless of previous experience with rocking or degree of
impairment, all children in both groups were successful at making the chair rock. The two
youngest children (both three years old) had some difficulty timing their efforts but were
able to make the chair rock. After some practice, their timing improved, but the amplitude
of rocking remained well below the chair’s full range of motion.
All children in both the SCI and TD groups were able to fit in the rocking chair.
The interchangeable seats and adjustable footrest accommodated most children without
alteration, but for those with shorter legs, it was necessary to insert padding between the
child and the seat back and, in one case, to place foam blocks on the footrest to enable
their feet to reach comfortably. This adjustment allowed them to engage in rocking but
made it more challenging to position them correctly.
Debriefing discussions following rocking sessions provided suggestions for
functional improvements to the rocking chair. These suggestions included a larger
footrest with straps and a non-slip surface to keep feet in place, and a mechanism to
prevent rocking during transfers or other activities.
62
Enjoyment: During conversation several of the children specifically said they
enjoyed rocking in the rocking chair, and two of the children, who had to return for a
second session due to problems with data collection, both expressed their eagerness to
return. Another indication of enjoyment was that many of the children rocked
spontaneously while not specifically engaged in a rocking task, and in some cases, it
was difficult to convince them to sit still.
Table 10: Participant experience while rocking
Participant
ID Description
Nervousness
Discomfort
Trunk
Movement
Leg
Use
Seat
Size
Footrest
Height
(cm)
Added
back
padding
(cm)
Added
seat
padding
(cm)
P15 Initially nervous, but confident by end of session Y N None Y S 15 0 0
P21 Very focused on completing rocking tasks; said she might
use the chair at home if she had one, and her mom used to
rock her when she was sick
N N Counter Y L 0 5 2
P23 Pretended to be in rocking boat; asked many questions;
spontaneous rocking between trials, but a little tired by end
N N Sync N S 15 0 0
P32 Focused on tasks; Helped with EMG placement N N Sync N S 0 0 0
P34 Commented rocking was fun; spontaneously rocked
between trials
N N Sync N L 7 0 0
P215 Enjoyed pushing with legs. Said seat was too narrow N Y None Y S 0 0 0
P187 Difficulty timing efforts, but made chair rock, and
improved over course of session
N N Counter N S 24* 8 0
P188 Vigorous rocking, but tired by end of session N N Sync Y S 15 7.5 0
P216 Returned for 2nd session, and parent mentioned they had
purchased a rocking chair for home use
N N None Y L 0 4 0
P217 Played with toys during rocking N N Counter N S 15 10 0
P204 Returned for 2nd session due to data collection error, and
parent commented “he couldn’t wait to come back here and
do this”; child said he would rock at home if he had a
rocking chair this cool
N Y Sync N L 0 0 0
*Included 9 cm block on top of footrest; Y= Yes, N= No, Sync = Movement synchronized with rocking so weight shifts forward during
forward chair movement; Counter = Trunk movement counter to rocking so weight shifts back as chair moves forward; S = Smaller seat; L
= Larger seat

63
There were no major, negative reactions to the rocking chair. One of the children
did initially express some apprehension that the chair would tip over but was reassured
when the safety stops which limit chair tilt were demonstrated, and quickly gained
confidence as they rocked. Two of the children rocked vigorously at first but expressed
that they were feeling tired toward the end of the rocking session.
4.3.3 Observed Trunk Motion During Rocking
The majority of children in the SCI group moved their trunk and/or head in time
with the rocking cycle. Of these, five leaned their head and upper trunk, shifting their
weight forward while the seat moved forward, and shifting their weight back while the
chair moved back. In contrast, three children instead moved their trunk in a
counterbalance rocking strategy, leaning forward from the waist as the seat of the chair
moved back. This effectively kept the center of mass of the seat/child in approximately
the same place but moved the seat back and forth. Finally, three children maintained a
mostly stationary trunk.
4.3.4 Increase in Muscle Activation During Rocking
Mean RMS muscle activation during rocking was significantly higher than during
quiet sitting (p < 0.05) for all twelve muscles tested in both SCI and TD groups, see
Table 9 and Table 10 respectively.
64
Table 11: Increase in muscle activation while rocking for children with SCI
Muscle n
Baseline:
Median[IQR]
Rocking:
Median[IQR]
Median Increase
(CI*) p-value†
Cervical PS‡8 6.40[4.39, 13.2] 14.1[11.0, 35.0] 7.14(3.92 to 27.0)* 0.006
Thoracic PS 11 5.60[3.59, 9.08] 18.3[12.8, 37.7] 12.8(1.46 to 32.8) 0.006
Lumbar PS 11 3.78[3.40, 5.60] 9.49[5.43, 21.5] 6.13(0.56 to 21.1) 0.006
Pectoral 11 5.15[3.37, 10.7] 10.8[7.79, 19.8] 4.49(1.14 to 19.6) 0.006
Biceps 11 4.01[3.24, 5.66] 16.0[7.30, 30.1] 13.0(3.46 to 79.1) 0.006
Triceps 11 3.37[3.23, 6.20] 18.0[10.5, 34.3] 14.2(6.50 to 31.2) 0.006
Rectus Abdominis 11 3.58[2.92, 3.82] 6.76[3.57, 14.3] 3.56(0.45 to 15.4) 0.006
Oblique 11 4.01[3.28, 4.64] 10.0[4.79, 13.3] 3.82(1.00 to 10.6) 0.006
Rectus Femoris 11 3.13[2.81, 3.26] 3.84[3.42, 13.4] 0.71(0.42 to 25.1) 0.006
Hamstring 11 3.21[2.85, 3.31] 4.45[3.78, 13.5] 1.29(0.50 to 21.9) 0.006
Tibialis 11 3.17[2.75, 4.19] 3.54[3.14, 18.0] 0.44(0.37 to 8.18) 0.006
Gastrocnemius 11 2.98[2.70, 3.88] 3.69[3.22, 9.68] 0.86(0.36 to 10.1) 0.006
All muscles tested showed a significant (p < .05) increase in muscle activity (as measured by mean of
EMGRMS) while rocking vs. baseline during quiet sitting in rocking chair immediately prior to rocking; †p-
values corrected for multiple hypotheses using the Holm-Sidak method; ‡Due to discomfort, 3 children
did not use cervical paraspinal EMG sensors; *the confidence level was set to 95%; however, due to the
nature of the non-parametric signed rank test and algorithms used by the Prism 10 software used, 98.8%
and 97.9% CI were output for SCI and TD groups respectively for all muscles except for cervical
paraspinals where 99.2% CI were output for both groups; PS = Paraspinal; CI = confidence interval; IQR
= Interquartile range;
Table 12: Increase in muscle activation while rocking for TD children.
Muscle n
Baseline:
Median[IQR]
Rocking:
Median[IQR]
Median Increase
(CI) p-value†
Cervical PS‡8 6.86[5.37, 9.77] 17.0[11.3, 22.8] 8.09(4.80, 18.4)* 0.012
Thoracic PS 10 5.28[4.87, 6.40] 13.1[9.62, 21.5] 8.13(2.76, 20.4) 0.012
Lumbar PS 10 3.35[3.12, 3.90] 8.39[6.04, 13.6] 5.20(1.04, 10.1) 0.012
Pectoral 10 3.97[3.47, 5.33] 5.86[4.54, 11.7] 2.04(0.58, 9.15) 0.0137
Biceps 10 3.37[2.89, 4.19] 5.42[3.90, 7.96] 1.17(0.34, 5.22) 0.0136
Triceps 10 3.64[3.24, 4.81] 7.59[4.16, 8.81] 3.17(0.45, 5.79) 0.012
Rectus Abdominis 10 3.19[2.94, 3.50] 5.19[4.31, 7.43] 2.01(0.52, 5.84) 0.012
Oblique 10 4.13[3.33, 4.25] 6.76[5.13, 9.91] 2.80(0.99, 6.57) 0.012
Rectus Femoris 10 3.07[2.98, 3.62] 4.99[3.85, 6.83] 1.68(0.55, 6.67) 0.012
Hamstring 10 3.41[3.00, 3.87] 11.9[9.69, 18.9] 8.90(3.05, 19.3) 0.012
Tibialis 10 3.33[2.90, 4.96] 18.9[15.1, 29.0] 15.8(7.44, 25.8) 0.012
Gastrocnemius 10 2.81[2.52, 3.35] 5.75[4.38, 11.8] 2.79(1.46, 19.7) 0.012
All muscles tested showed a significant (p < .05) increase in muscle activity (as measured by mean of
EMG in µVRMS) while rocking vs. baseline during quiet sitting in rocking chair immediately prior to
rocking; ; †p-values corrected for multiple hypotheses using the Holm-Sidak method; ‡Due to discomfort,
2 children did not use cervical paraspinal EMG sensors; *the confidence level was set to 95%; however,
due to the nature of the non-parametric signed rank test and algorithms used by the Prism 10 software
used, 98.8% and 97.9% CI were output for SCI and TD groups respectively for all muscles except for
cervical paraspinals where 99.2% CI were output for both groups; PS = Paraspinal; CI = confidence
interval; IQR = Interquartile range

65
Muscle activation is measured by the increase from baseline of EMG amplitude
(VRMS). Due to discomfort, cervical paraspinal sensors were not used on several
participants in each group leading to a smaller n for this muscle, and a different
confidence interval. Median increase and confidence interval are shown for all.
4.3.5 Temporal Muscle Activation Patterns
Typical temporal muscle activation patterns during the rocking cycle for both SCI
and TD groups are shown in Figure 14.
Figure 14: Averaged muscle activation during rocking in children.; x-axis is one full
rocking cycle; y-axis is normalized to the amplitude of EMGRMS in the rocking cycle;
n.u. = normalized units

66
General trends indicate that many of the muscles exhibit similar activation
patterns between the groups but are often out of phase with each other. For instance,
cervical and thoracic paraspinals show very similar activation curves, but in the SCI
group, the peak activation occurs earlier in the rocking cycle. Other muscles have
maximum activations that occur close to the same point in the rocking cycle but exhibit
different shaped curves. For example, both the SCI and TD groups show maximum
activation of the rectus abdominis at the same point in the rocking cycle, but the SCI
group has a much broader activation peak than the TD group. Table 13 describes the
observed locations of peak muscle activation and the effects of muscle activation with
respect to the rocking cycle in SCI and TD groups.

Table 13: Observed actions of muscles during rocking in children with SCI.
Max Activation
Location
(% of cycle)
Muscle SCI TD Curve comparison Muscle Action
Cervical
Paraspinal
73%
(Mid FW)
93%
(Late FW)
Similar shape; SCI peak occurs earlier in cycle Stabilizes trunk, resists forward motion, and shifts weight back to
assist in rocking
Thoracic
Paraspinal
70%
(Mid FW)
89%
(Late FW)
Similar shape; SCI peak occurs earlier in cycle Stabilizes trunk, resists forward motion, and shifts weight back to
assist in rocking
Lumbar
Paraspinal
74%
(Mid FW)
93%
(Late FW)
SCI peak occurs earlier in cycle with secondary peak in BW phase Stabilizes trunk, resists forward motion, and shifts weight back to
assist in rocking
Pectoral 60%
(Late FW)
38%
(Late BW)
SCI peak occurs later in cycle Pull on arm rests as chair reverses direction at back of cycle
Biceps 50%
(Late BW)
42%
(Late BW)
Very similar curves with single peak occurring close to direction
reversal at back of cycle
Stabilizes and shifts weight forward at the end of back swing
Triceps 74%
(Mid FW)
85%
(Mid FW)
Max activation close to the same point, but TD has secondary peak
in late BW phase, and SCI does not.
Stabilizes and shifts weight backward at the end of front swing
Rectus
Abdominis
53%
(Mid BW)
36%
(Mid BW)
Max activation at similar location, but SCI has broader peak Stabilizes trunk and shifts weight forward in preparation for
reversal of direction
Oblique 25%
(Mid BW)
40%
(Mid FW)
Max activation occurs during backward motion, but SCI peak
occurs earlier in cycle
Stabilizes trunk and shifts weight forward in preparation for
reversal of direction
Rectus
Femoris
5%
(Early
BW)
41%
(Late BW)
SCI peak occurs as chair reverses direction at front of cycle; TD
peak occurs just before back of cycle
Flexes hip
Hamstring 30%
(Late BW)
66%
(Early
FW)
TD and SCI both have secondary peaks that occur close to each
other’s primary peaks
Straightens hip as chair moves back
Tibialis
Anterior
70%
(Mid FW)
71%
(Mid FW)
SCI and TD peaks both occur mid FW motion, but SCI peak is
broader
Lifts front of foot to avoid impeding forward motion
Gastroc 19%
(Mid BW)
32%
(Mid BW)
SCI peak that spans from before to after direction reversal at front
of cycle. TD slightly later.
Push on footrest during backward motion
FW = Forward motion phase of rocking cycle; BW = Backward motion phase of rocking cycle; Early = first third of motion in FW or BW direction; Mid = middle third of
motion in FW or BW direction; Late = last third of motion in FW or BW direction
65
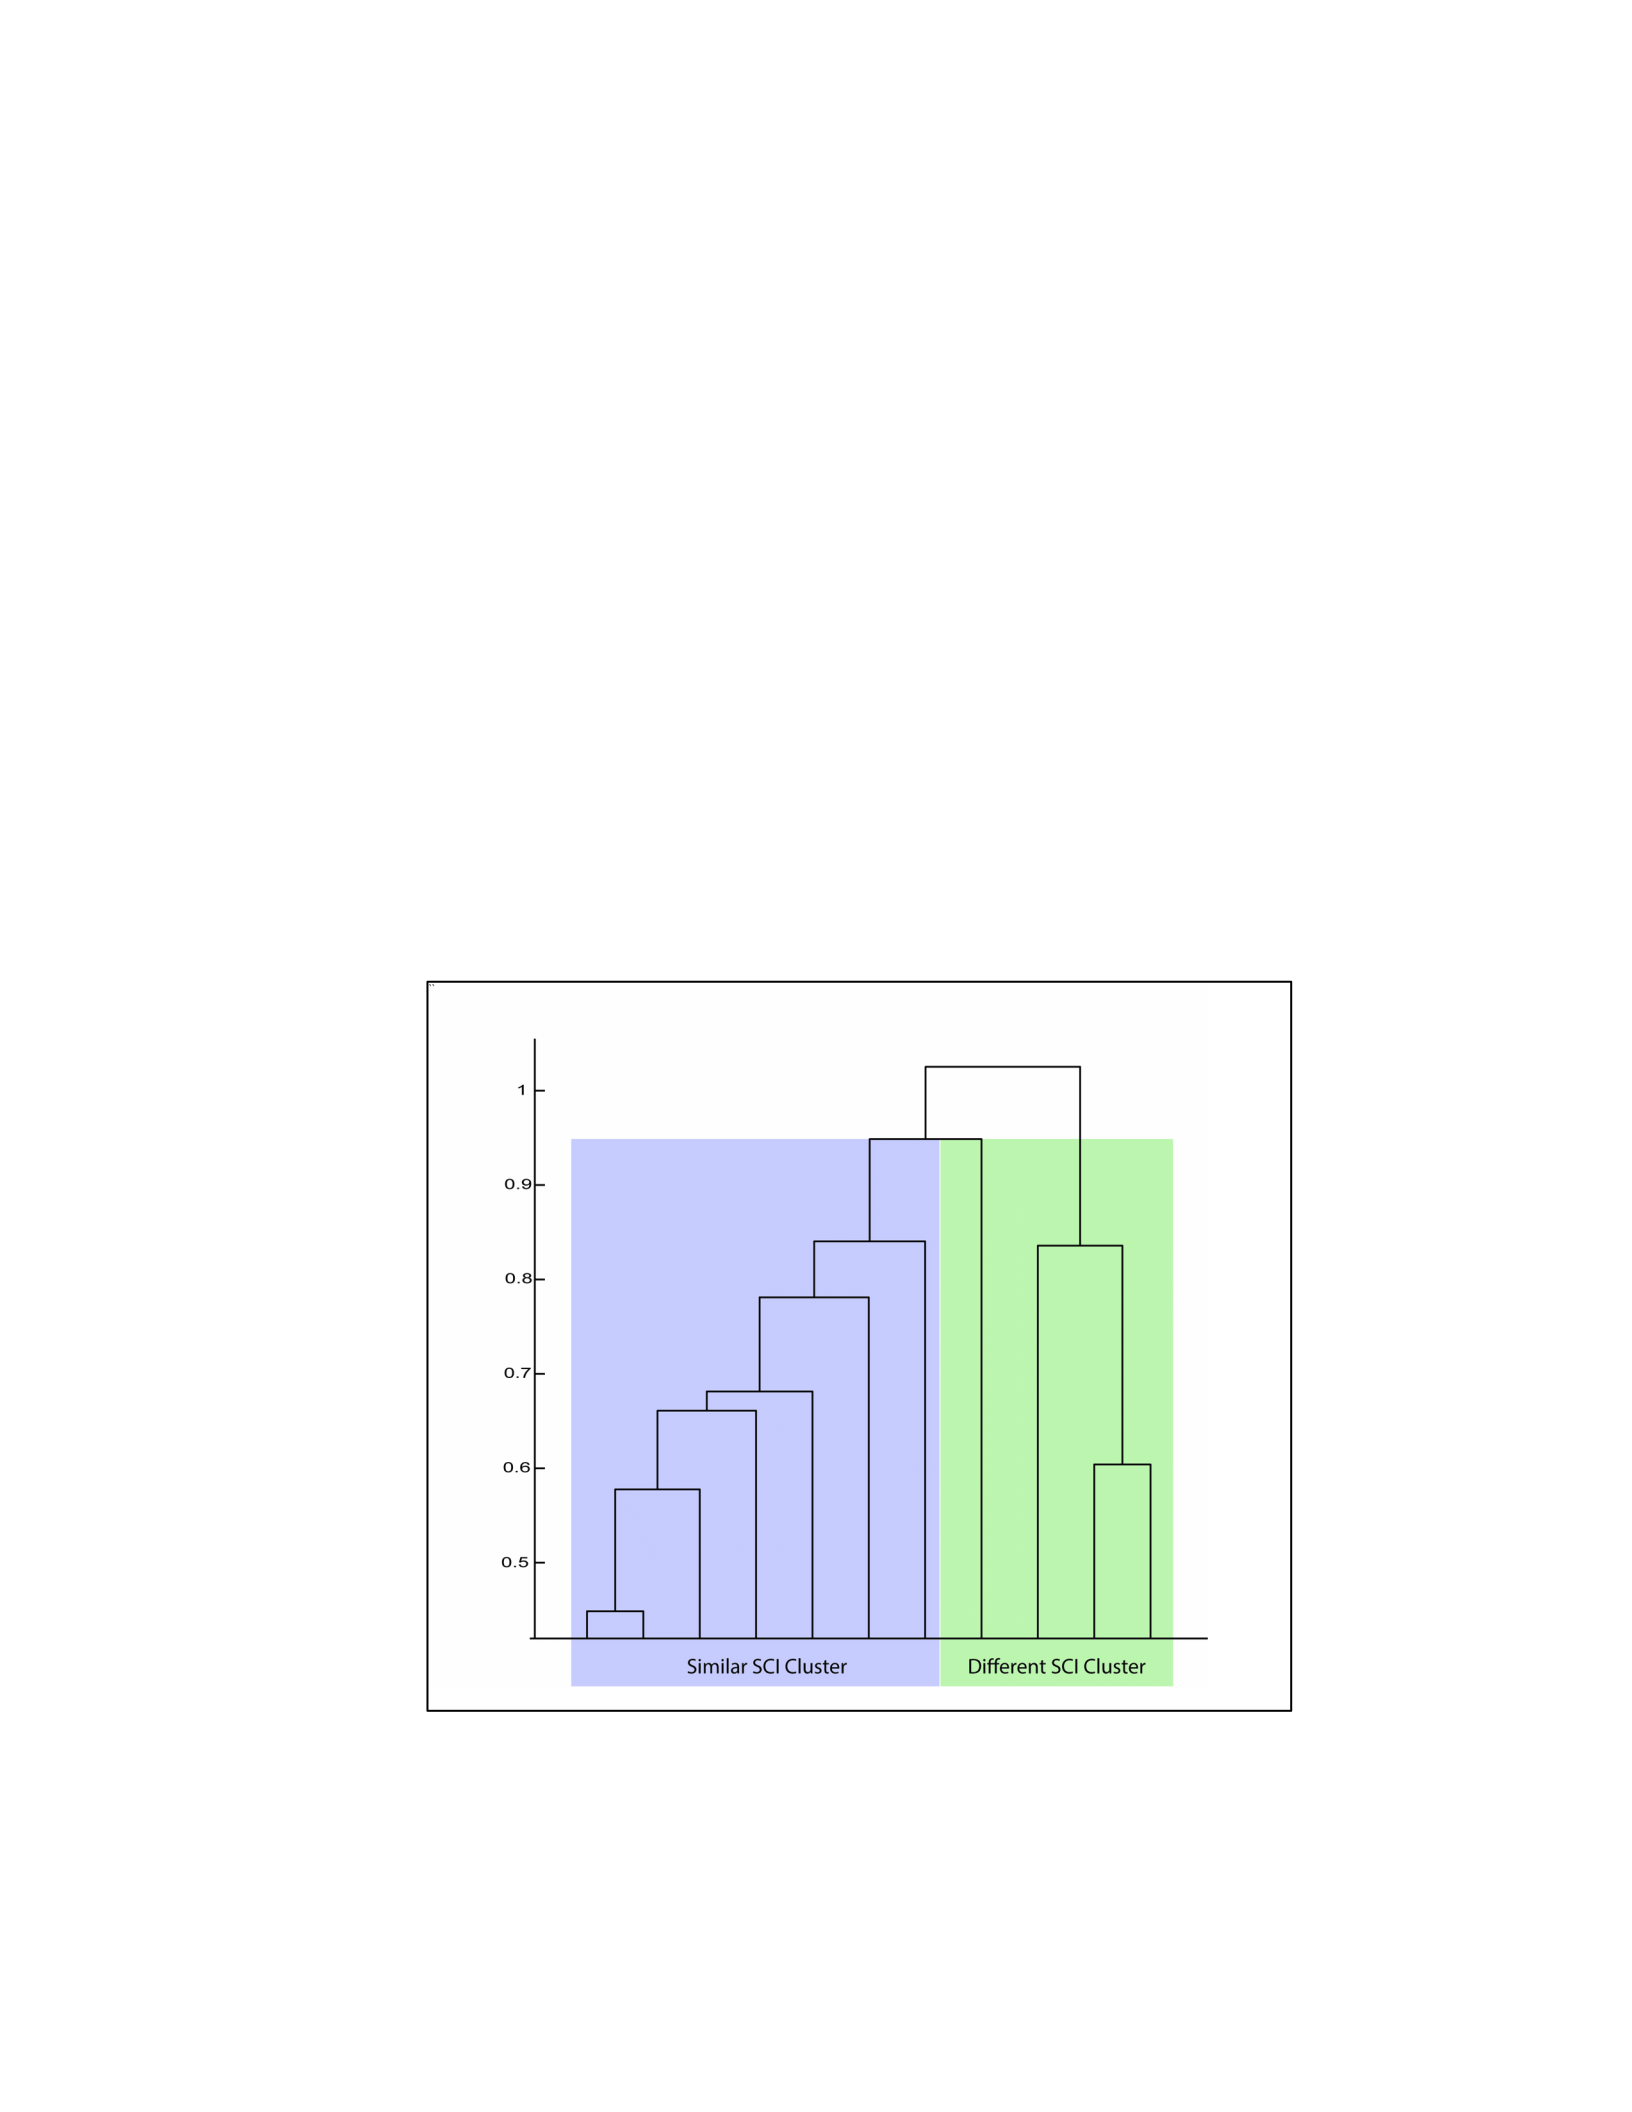
66
Cluster analysis based on the timing of muscle activation divided the SCI group
into two clusters of seven and four subjects as shown in the dendrogram in Figure 15.
The average calculated distance from the seven and four-subject clusters to the TD group
was 0.78 and 1.16 respectively. Thus, the seven-subject cluster was labeled the “TD-
similar cluster”, and the four-subject cluster was labeled the “TD-dissimilar cluster”.
Plots of the clustering data for the trunk muscles are shown in Figure 16. This
figure illustrates that, for most trunk muscles, the temporal activation patterns in the TD-
similar cluster are closely comparable to those of the TD group, whereas the patterns of
the TD-dissimilar group are not.
Figure 15: Dendrogram showing clusters based on average normalized EMG
amplitude in each rocking cycle quartile for trunk muscles.
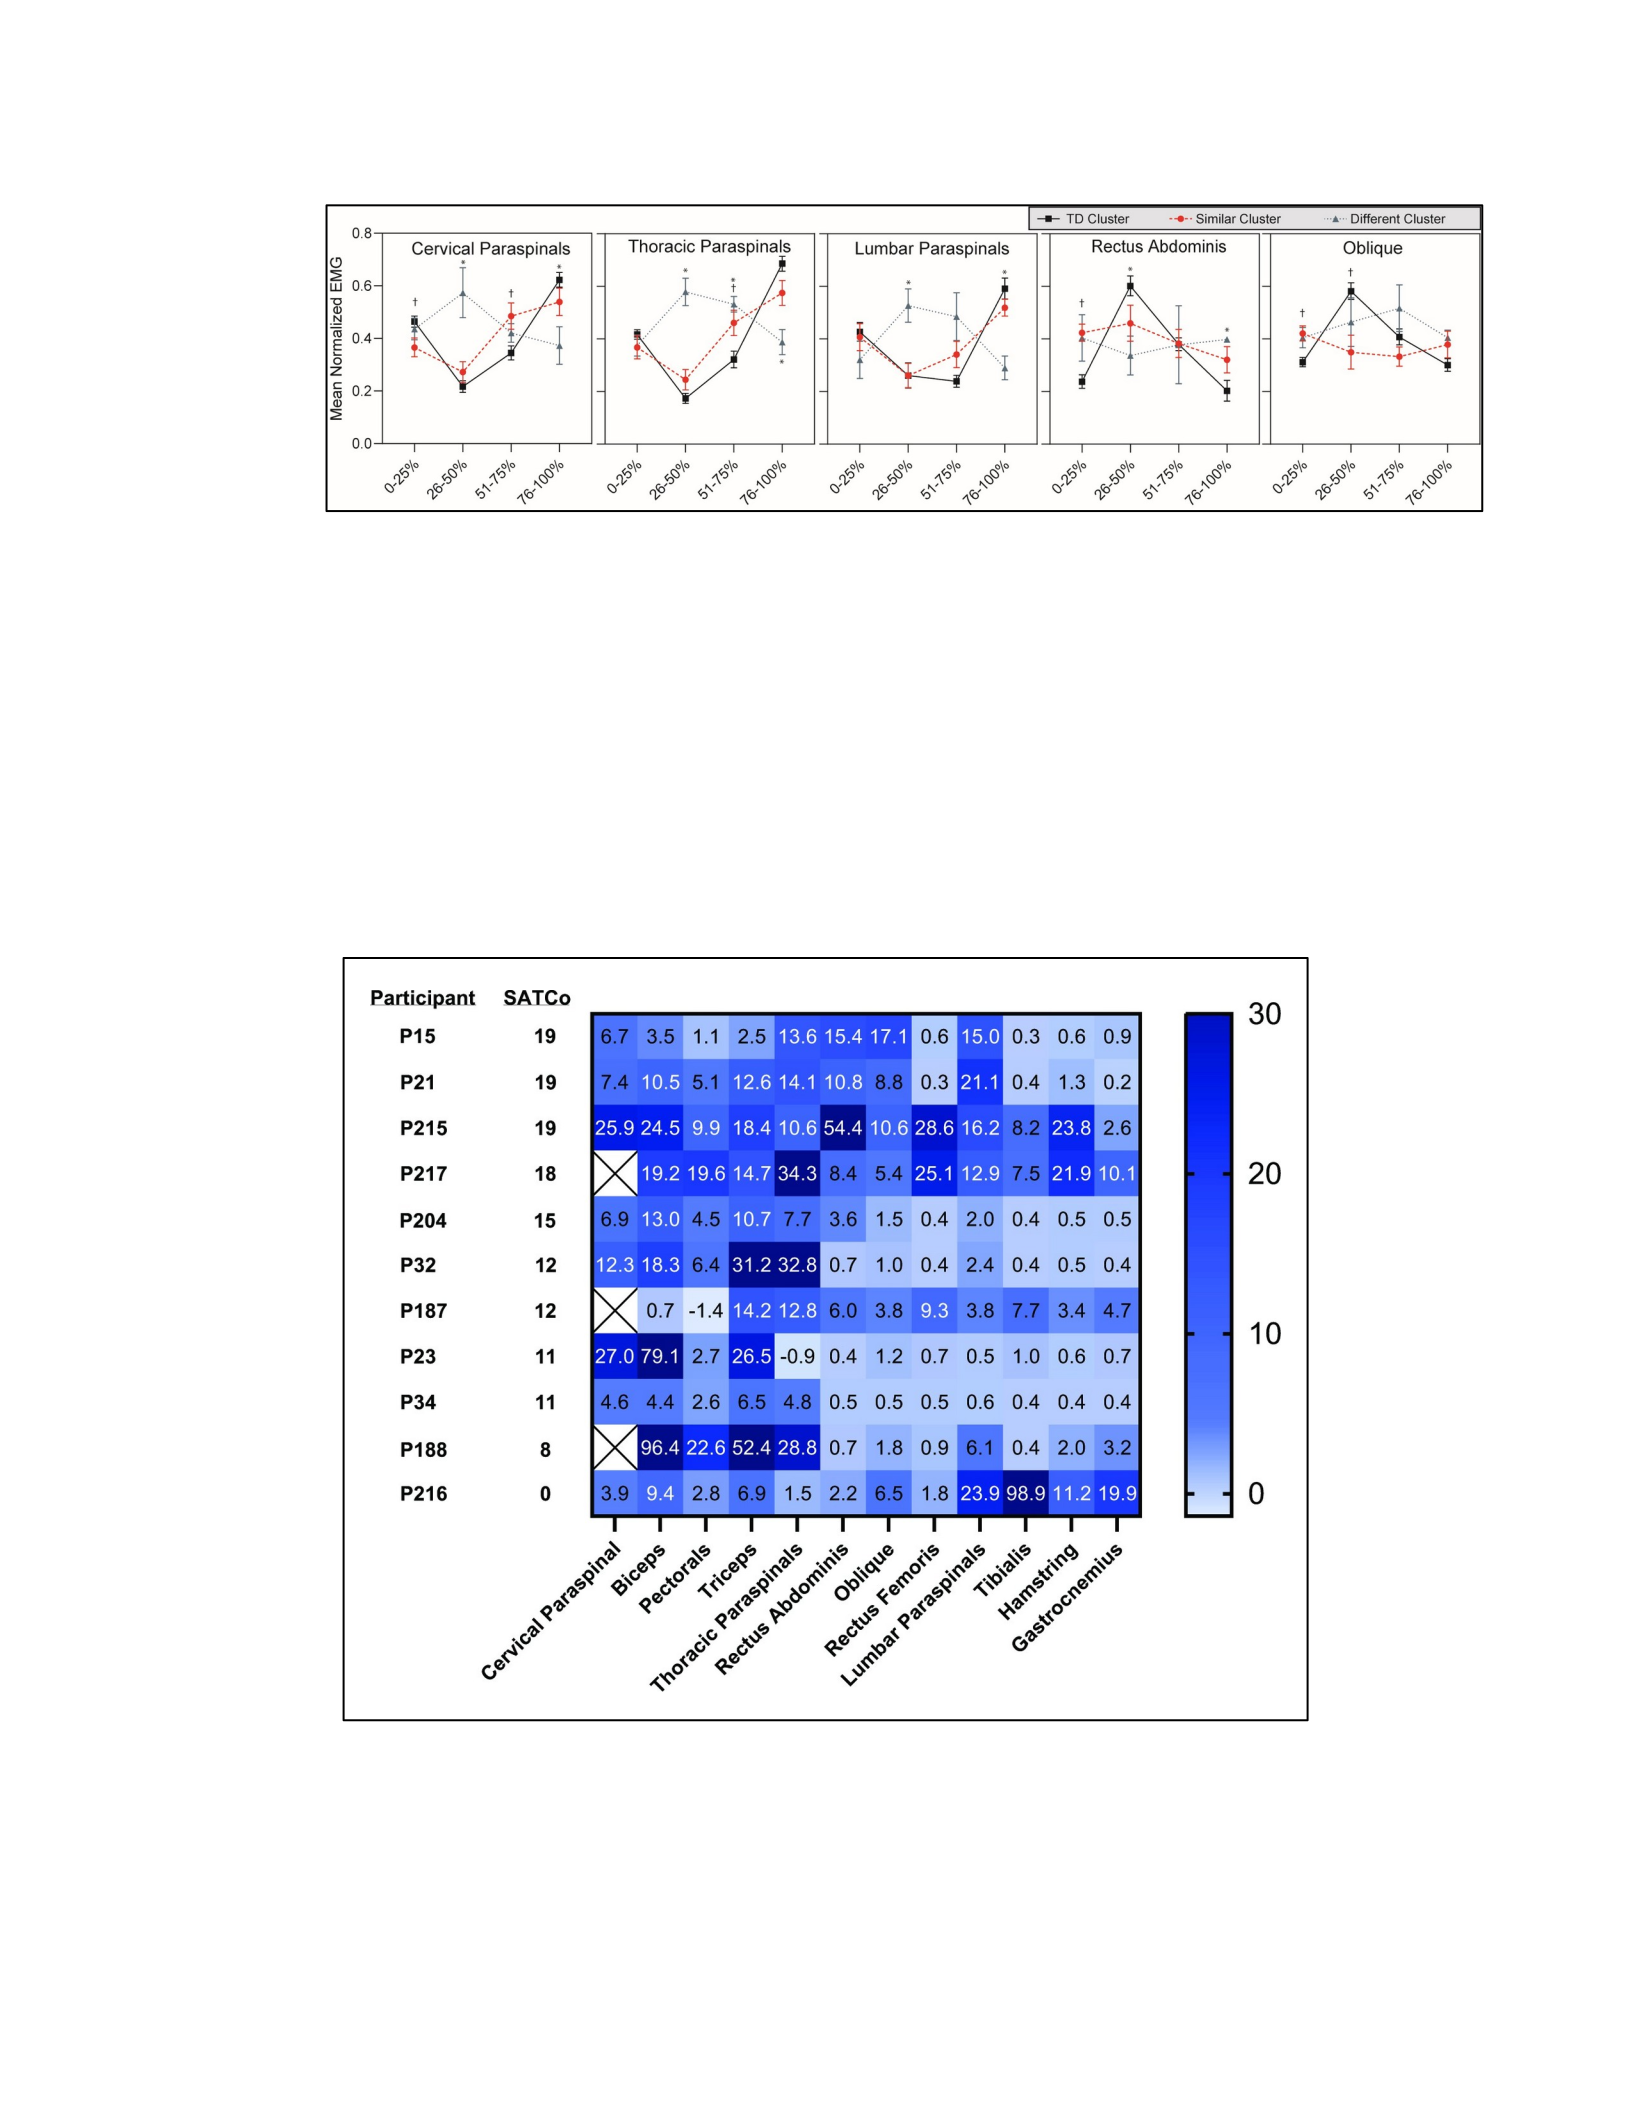
67
Figure 16: Average normalized EMG amplitude in trunk muscles during each quarter of the
rocking cycle for the TD cluster and two SCI clusters; *significant difference between
different cluster and TD cluster; †significant difference between similar cluster and TD
cluster
4.3.6 Muscle Activation Amplitude
Figure 17 shows a heatmap of muscle activation in each muscle as measured by
mean EMG amplitude (VRMS) during rocking. Each row represents one child, and each
Figure 17: Muscle activation (µVRMS) heatmaps for SCI group. ; Higher numbers and
darker colors represent higher activation; Muscles are on x axis, sorted by spinal cord level
of nerve roots. Y axis shows SATCo score, representing trunk control. SATCo =
Segmental Assessment of Trunk Control

68
column represents one muscle. Muscles are sorted from left to right in a cephalocaudal
direction. For children with SCI, the rows are sorted by SATCo score.
Results of Spearman correlation analysis of SATCo vs. muscle activation
amplitude for the SCI group are presented in Table 14. No significant correlation is
observed for cervical or thoracic paraspinals, but a significant positive correlation is
observed for rectus abdominis (r = 0.89, p = 0.003), oblique (r = 0.73, p = 0.03), and
lumbar paraspinals (r = 0.68, p = 0.05), indicating that participants with higher SATCo
scores show higher activation in muscles lower on the trunk than those with lower
SATCo scores.
Table 14: Activation amplitude during rocking vs. SATCo score
Participant SATCo
Cervical
Paraspinal
(µVRMS)
Thoracic
Paraspinals
(µVRMS)
Rectus
Abdominis
(µVRMS)
Oblique
(µVRMS)
Lumbar
Paraspinals
(µVRMS)
Mean TD 20 9.5 10.1 2.8 3.5 6.9
P15 19 6.7 13.6 15.4 17.1 15.0
P21 19 7.4 14.1 10.8 8.8 21.1
P217 18 NA†34.3 8.4 5.4 12.9
P204 15 6.9 7.7 3.6 1.5 2.0
P32 12 12.3 32.8 0.7 1.0 2.4
P187 12 NA†12.8 6.0 3.8 3.8
P23 11 27 -0.9 0.4 1.2 0.5
P34 11 4.6 4.8 0.5 0.5 0.6
P188 8 NA†28.8 0.7 1.8 6.1
Spearman’s r -0.18 0.30 0.89 0.73 0.68
P (two-tailed) 0.74 0.42 0.003* 0.03* 0.05*
*Significant difference (p<.05); †Cervical EMG sensors not used due to participant
discomfort; SATCo = Segmental assessment of trunk control, RMS = root mean square

69
4.4 Discussion
Of primary importance, the results confirmed our first hypothesis that trunk
muscle activation would increase above baseline during rocking. In fact, all muscles
tested in both TD and SCI groups showed significantly higher levels of activation during
rocking than at baseline. These results suggest that, in addition to activating trunk
muscles and being helpful for children with poor trunk control, rocking may also be a
useful activity for activation of leg muscles in children with SCI. Some children who can
activate leg muscles may still not be ambulatory due to weakness, poor balance, or
inability to manipulate an assistive device. Rocking may be an accessible form of
enjoyable, voluntary movement to use available trunk and leg muscles.
Our second hypothesis of differences between trunk muscle activation during
rocking by children with SCI and TD children was in part confirmed by cluster analysis
of temporal activation of muscles during the rocking cycle. This revealed two muscle
activation patterns, a pattern similar to TD and a pattern dissimilar to TD, providing
insights into the motor strategies employed by children with SCI during rocking. One
notable finding was the higher variability in muscle activation patterns in the SCI group,
and the presence of synchronous and counterbalance rocking strategies employed by the
children with SCI. These different rocking strategies are at least partially reflected in the
cluster analysis. For instance, three of the four subjects in the “TD-dissimilar” cluster
used the counterbalance strategy to rock, while none of those in the “TD-similar” cluster
used this strategy.
There is also a possible relationship between optimal fit in the rocking chair and
rocking styles. Both of the children with poor fit that could not be completely corrected

70
via padding or other adjustments were in the “TD-dissimilar” cluster, and all the children
in the dissimilar cluster (P216, P21, P187, and P217) needed extra padding on the
footrest, behind the back, or both due to issues with fit. In contrast, the “TD-similar”
cluster only contained one child who needed additional padding (P188 with 7.5 cm of
padding behind her back). Since the smallest and largest children were the most likely to
need extra measures to achieve good fit, it is also possible that both the issues with fit and
the differences in temporal muscle activation patterns were due to their size. Further
research will be needed to clarify the question of proper fit relating to meaningful muscle
activation.
A significant association was observed between trunk control, as measured by
SATCo score, and activation of muscles lower on the trunk. This matches expectations,
since higher SATCo scores reflect greater control and activation of trunk muscles in
lower thoraco-lumbar areas. It should be noted that the two subjects with AFM were
excluded from this analysis, since there is not a clear, level-dependent pattern of
impairment with this etiology.
Primary motivations for investigating the use of a rocking chair in this population
include accessibility and enjoyment. Importantly, there were no injuries during testing,
and the identified safety concern has been addressed by repositioning a cross brace so
that it no longer presents a potential to be a pinch point. It was found that all children
included in the study were able to make the chair rock, regardless of previous experience
or impairment. Feedback from children and parents during rocking also demonstrated that
the children enjoyed rocking in the chair and were motivated to use their muscles to make
it rock. These factors demonstrate that rocking gives children with SCI an enjoyable

71
opportunity to move independently, which may be rare outside use of a wheelchair for
mobility and thus particularly motivating for them.
4.4.1 Limitations
The results highlighted in this study should be interpreted considering identified
limitations. As noted previously, there were several sources of noise in the EMG data
used for this analysis. While all of these were addressed, it is important to acknowledge
that this does introduce some additional uncertainty regarding the accuracy of some of
the source data.
Additionally, the SATCo scores of the participants, which indicate their inherent
trunk control, ranged from 0 to 19. However, the distribution skewed towards higher
SATCo scores. Ideally, a more balanced distribution of SATCo scores would have been
preferred to ensure a broader representation of participants across the entire spectrum of
trunk control abilities.
While all children were able to rock, fit in the rocking chair may have had an
effect on muscle activation patterns, especially in cases where the balance of the rocking
chair was significantly shifted away from its normal neutral position, and this may have
effected the muscle activation patterns in some children, and influenced some results.
4.4.2 Future Work
In future research, enrolling children with a greater range of SATCo scores may
better quantify the relationship between trunk control and muscle activation patterns
during rocking and allow for exploration of additional strategies to activate the desired
muscles for rocking. For example, redesigning the footrest to attach to the seat of the

72
chair instead of the base could target the use of trunk muscles, as it would prevent use of
leg muscles initiating rocking by pushing the footrest. Additionally, asking children to
take their arms off the armrests could encourage the use of trunk muscles for weight
shifting stabilization during the forward and backward phases the rocking cycle.
Future work should also that the participants fit with the rocking chair may affect
the resulting muscle activation patterns. In addition to defining what constitutes
acceptable fit, parameters to fully characterize fit, such as chair balance point, footrest
height, and seat position should be defined and recorded. This data could then be
included in any analyses performed to learn how it affects rocking.
Investigating the long-term use of rocking chairs in the home would be valuable
to understand the different rocking strategies employed by children with SCI and the
progression of neuromuscular activation and capacity. Chairs could also be equipped
with sensors to monitor rocking performance, including parameters such as time spent
and amplitude of rocking. Sensors could also be installed to detect forces applied to the
rocking chair and provide valuable information about the muscles being utilized by the
child during rocking. Other possible uses of sensor data would be to adjust the difficulty
of rocking to provide extra resistance or help depending on the needs of the child, or to
provide feedback in the form of a game to encourage the use of target muscles.
4.5 Conclusions
Rocking in this prototype glider rocking chair activates the neuromuscular system
and is an accessible activity for children with varying degrees of trunk impairment due to
SCI. Additionally, the study provides the first examination of the timing and amplitude
of muscle activation during rocking, and the differences between the TD and SCI groups.

73
These results, together with the observation that the rocking chair prototype is safe and
enjoyable for use by children in this population, highlight the potential of rocking chair-
based interventions as an effective approach for trunk muscle activation and a promising
component of extending ABT in children with SCI beyond the clinic to the home and
community.

74
CHAPTER 5
MUSCLE ACTIVITY PREDICTION FROM EMBEDDED SENSORS
5.1 Introduction
In children with SCI, lack of trunk control due to neuromuscular paralysis/paresis
has been shown to increase the risk of secondary conditions such as scoliosis and
compromised lung function [3, 13, 17, 27, 28]. Recent research has shown that activity-
based therapy (ABT) is effective at improving trunk control in this population [33]. In
order to address the need for children to continue to activate trunk muscles in the home, a
rocking chair designed for children with SCI, and been designed, built and tested as
described in chapter 3 [59].
To validate that rocking in this rocking chair activates muscles, TD children and
children with SCI rocked in the chair while muscle activity was measured using EMG.
As described in Chapter 4, comparisons were drawn between muscle activation patterns
in the two cohorts, and it was established that muscle activity during rocking is
significantly higher than at baseline for muscles in arms, legs, and trunk.
The current chapter will build on this previous work by incorporating various
sensor technologies into the chair to provide feedback to therapists about user activity
while rocking in the rocking chair. For example, sensors in the chair would enable
therapists to track basic use factors such as rocking duration and amplitude.
Appropriately located force sensors would be used to monitor specific activity of the
limbs and trunk and therefore may eliminate the need to use EMG which, while an

75
accepted standard for measuring muscle activity, is expensive and requires training.
Information about the which muscles are employed by the child to make the chair rock,
as well as insight into the ways muscle use patterns change over time would provide
useful information for therapists interesting in longitudinal tracking of improvements
provided by muscle activation activities. By adding multiple sensors in strategic
locations to measure forces applied to the rocking chair and body movements initiated by
the child, a variety of rocking activity data can be collected.
Initially, specific aim 4 focused on using sensor data to develop methods to
predict SATCo score using multivariate linear regression analysis. As the project
progressed, this was found to be problematic since each child only provided a single data
point with respect to SATCo score and not all SATCo scores were represented in the
dataset. Additionally, correlations between sensor data and trunk muscle activation were
too complex for standard linear regression techniques to be effective. To address these
difficulties, machine learning techniques were implemented, and the focus was shifted
from predicting SATCo score, to predicting muscle activation during rocking.
5.1.1 Study Rationale
In this chapter, data recorded from sensors embedded in the prototype rocking
chair will be used to quantify chair and participant motion, as well as forces applied by
users to train machine learning models in an attempt to infer subject muscle activations
during rocking. Machine learning techniques used in this research will include both
established regression learning and neural network model techniques.

76
5.1.2 Machine Learning Application to Chair Sensors
Biomechanical modeling using inverse dynamics calculated from 3-dimensional
motion capture and force-plate data has been used to assess loads on internal anatomical
structures including joints and muscles [64]. In the context of rocking in the home,
however, biomechanical modeling cannot easily be used to quantify muscle activation
forces. This challenge stems from multiple factors, including the requirement for costly
motion capture systems, which are not available in the home or even in most clinical
settings, and the need for accurate measurements of multiple reaction forces on the
rocking chair. Additionally, factors such as the need for custom biomechanical modeling
for each child, and complicated setup procedures for each rocking session complicates
this approach.
For similar situations where motion capture and/or force plate data cannot be
obtained, machine learning methods have been used to aid in biomechanical analyses
[64]. Examples include estimation of ground reaction forces based on body-worn
accelerometer data [65, 66] and estimation of voluntary elbow torque based on EMG and
kinematic data [67]. In addition to analysis of biomechanical problems, machine learning
techniques have been used to draw inferences based on data from sensors embedded in
equipment used by patients. An example of this is the use of Logistic Regression and
Feed Forward Neural Networks to categorize the orientation of patients in bed based on
data from load cells positioned under the legs of the bed. This system could help to
reduce the incidence of pressure sores by alerting caregivers when a patient’s position
has not changed after a prescribed period of time [68].

77
5.1.3 Regression Learning
Regression learning is a supervised learning technique that is used to find the
correlation between independent input variables and a dependent output variable. In this
work, ensemble learning, which utilizes multiple regression models to learn relationships
between a set of features and a response, will be used. These models are then combined
to produce a stronger learner with improved generalization performance. The base
learner that was selected for this work is the decision tree, and boosting was chosen as
the approach to constructing the composite learner. Boosting is an incremental learning
process for constructing the composite learner, in which new learners compensate the
error from previous learners. [69]
5.1.4 Neural Networks
Briefly, a neural network is a common machine learning model built from layers
of interconnected artificial neurons. A typical neural network consists of an input layer,
an output layer, and one or more hidden layers. Neurons in each layer are interconnected
nodes with neurons in neighboring layers, and weights are assigned to these connections
[70]. Training of a neural network involves adjusting these weights to minimize the error
between the predictions and the actual targets. Learning algorithms, such as
backpropagation, where errors are propagated back through the network from the output
layer to reduce overall error, are used to adjust weights. Regularization techniques can
also be applied to prevent overfitting, which causes the model to perform well on training
data, but poorly on new data. Regularization can help maintain smaller weights and
produces models that are better at generalizing to new data [71].

78
Using these techniques, models will be trained to infer muscle activation in 12
individual muscles in the user’s arms, legs, and trunk. Finally, the performance of the
model will be compared against individual sets of activity data to evaluate efficiency of
predicting activation of specific muscles during rocking by SCI patients evaluated under
IRB approval.
5.2 Materials and Methods
5.2.1 Participants
Participants for this analysis were the same as detailed in sections 4.2.1, 4.2.2, and
4.3.1, and were enrolled under University of Louisville IRB #17.0725. Two cohorts were
enrolled: children with SCI and TD children. EMG data collected from these participants
(as detailed in section 3.2.4) was also used in this analysis.
5.2.2 Rocking Chair Instrumentation
As detailed in Chapter 3, the prototype rocking chair was designed to include
embedded sensors which could capture forces applied to different parts of the rocking
chair, and movement of the seat and the subject’s trunk during rocking. Sensors used,
sensor locations, and data captured are shown in Table 13.
Single zone force sensitive resistors were installed on the arm rests (Walfront
SF15-150 Force Sensitive Resistor, sensitivity range 0.1 – 100N), and in the seat of the
chair (Interlink Electronics FSR® Model 406, sensitivity range 0.1 – 10N) to track forces
applied during rocking. In order to increase the sensitivity of the FSRs, actuators were
designed, and 3D printed to concentrate the applied force. For instance, the actuator for
the arm rest FSR (Figure 18) sat between the armrest cushion and the FSR and helped to
ensure that force applied to any part of the cushion would trigger a similar response from

79
the FSR. Similarly, the seat FSRs were mounted on a flexible 3D printed mat and 3D
printed actuator positioned over them to enhance their sensitivity to forces applied to the
seat padding overlaying them.
Table 15: Sensors used to collect data for training machine learning models
Sensor Name Sensor Type Measurement Taken
Footrest Four half-bridge load cells configured as
eight active element Wheatstone bridge
Force applied by feet to top of footrest
Right arm rest FSR under pad on right armrest Force applied to top of pad
Left arm rest FSR under pad on armrest Force applied to top of pad
Trunk Strap Optical Time of Flight sensor Elongation of strap around trunk as tension
is applied.
Position Rotary potentiometer driven by motion of
linkage arms
Seat position in rocking cycle
Seat Four FSRs in square array Force applied to each seat FSR
CoP Calculated from seat FSRs Forward/back movement of pressure
applied to the seat. Average of front FSRs
minus the average of back FSRs.
Accelerometer Accelerometer Acceleration parallel to swing of the
rocking chair
FSR = Force Sensing Resistor; CoP = Center of Pressure
The footrest was constructed of two sheets of Baltic Birch plywood, with four
recesses cut in the lower piece and load cells (SMAKN® Half Bridge Body Load Cell
Electronic Scale Weighing Sensor 50Kg) set into them. The top sheet of plywood was
then placed on top of these load cells and attached with screws which passed through
holes drilled in the lower sheet of plywood, which allowed the upper sheet to move
vertically, but constrained horizontal motion. This allowed any load placed on the footrest
to actuate the load cells. Load cells were connected in an eight active element Wheatstone
bridge configuration, and changes in voltage were read to measure the applied loads.

80
Figure 18: Armrest FSR with 3D Printed actuator
As previously detailed in section 3.5.3, a position sensor was constructed of a
rotary potentiometer (TT Electronics, P160KNP) installed on the base of the chair and
coupled to one of the chair’s rocker arms via spur gears. This setup can track the position
of the chair throughout its entire range of motion. The potentiometer is configured as a
voltage divider (5V input, 10k ohm fixed resistance, 10k ohm variable resistance), and
the voltage read from the center pin corresponds to the position of the chair.
To track trunk motion, a novel sensor was utilized. This sensor has been
described in detail in Lin et al [72], but briefly, consists of stretchable fibers with a
urethane core and a silicone cladding sandwiched between two pieces of elastic fabric
with the ends routed, via a 3d printed mounting block, to a 5 x 5 mm mirror oriented to
couple the fiber ends to the ports of a miniature time-of-flight (TOF) sensor for light
detection and ranging (LIDAR) (Pololu VL53L0X ToF sensor, Pololu Robotics and

81
Electronics). This

82
Figure 19: Optical stretch sensor on belt mounted on rocking chair
arrangement allows the TOF chip to detect elongation of the optical fiber as the fabric
is stretched. This sensor was attached to a belt (AliMed® Pediatric Walker Belt) using
hook-and-loop fasteners at each end, so that the elastic portion of the fabric would
elongate when tension was applied to the belt. This belt was attached to the seat back of
the chair as shown in Figure 19 and fastened around the trunk of the subject during
rocking so that trunk movement would stretch the optical fiber, producing a signal from
the TOF chip which was recorded. It should be noted that, as this sensor became
available after data had been collected from the first seven children with SCI. Data from
the strap is available for the last four children with SCI who were tested, and for all TD
children.
All sensors were connected to a custom PCB, which was designed to plug into
IO ports A and B on an NI myRIO 1900-(National Instruments, Austin, Texas) as shown
in Figure 20. Schematics are included in Appendix C. A load cell amplifier (SparkFun
Qwiic Scale NAU7802, Sparkfun Electronics, Niwot CO) was mounted on the PCB to
acquire data from the load cells in the footrest. I2C data from the load cell amplifier and

83
the TOF sensor were acquired by an Arduino Nano (Arduino.cc) mounted on the custom
PCB and relayed to the myRIO-1900 where all data was saved to file.
Figure 20: Custom PCB for data collection
5.2.3 Data Collection
sEMG data collected as previously detailed in section 3.2.4 was used to provide
the target data for training and testing the machine learning models. Data from sensors
embedded in the rocking chair was acquired at 40 Hz, and a pulse signal was recorded at
the beginning and end of each data capture session to facilitate synchronization between
the 2000 Hz sEMG data and the sensor data.
5.2.4 Regression Model Development
5.2.4.1 Data Processing and Feature Extraction
Four FSRs in the seat of the chair positioned in a square array were used to
generate an approximation of the center of pressure applied to the seat. This was
calculated by taking the average of the front FSRs minus the average of the back FSRs.
This gives a measure of fore-aft changes in pressure as the child rocks and can be used

84
to

85
detect weight shifts due to trunk movement. This data was treated as a separate sensor,
and features were extracted from it as well as from the individual seat sensors.
To synchronize the sEMG data with the sensor data, it was necessary to
increase the data rate of the sensor data to match the 2000 Hz rate of the sEMG data.
This was done with a custom MATLAB script (Appendix A) which identified the
beginning and end of each data collection in both data files using the synchronization
pulse, and the sensor data was interpolated to match the length of the sEMG data.
5.2.4.2 Artifact Removal and Rocking Cycle Creation
As detailed in section 3.2 artifacts were removed from sEMG data, and data was
broken into individual rocking cycles. Each rocking cycle was standardized to 1000 data
points in length, and sensor data was normalized by to the peak-to-peak amplitude of the
corresponding cycle using equation 1, similar to the method used previously in prototype
EMG cycle creation, and described in Elamary et al. [73, 74].
Features were extracted for each rocking cycle for use as inputs in training of the
regression model. The features listed in Table 14 were calculated based on data from
each sensor using a custom MATLAB script (Appendix A). Features were calculated as
follows. Points 1-10: The 1000 data points for the given cycle were coarse-grained down
to 10 points (P1 – P10) by stepping through the data 100 points at a time and taking the
average of those points. Thus, the first point (P1) represents the average of the first 100
points in the cycle, and P2 represents the average of points 101-200 and so forth. Area
under the curve was calculated numerically simply by summing the value of all 1000 data
points for the given cycle. Maximum and minimum values were simply the largest and

86
smallest data point in the given cycle. Average was calculated by taking the mean of all
data points in the cycle. Peak-to-peak amplitude was the difference between the
maximum and minimum values in the given cycle. Maximum and minimum locations
were simply the index (from 1 to 1000) of the maximum and minimum data points in the
cycle. RMS was calculated by taking the square root the mean of the squares of all data
points in the cycle. Maximum Sum and maximum sum location were calculated by
finding the value of the largest sum of 300 contiguous points, and the index of its center
point. Frequency points 1-10 (F1 – F10) were calculated by taking the power spectrum
between 0 and 6 Hz, split into 10 bins, with the value of each bin representing one
feature. Centroid of the power spectrum with respect to frequency was calculated by
dividing the sum of the ten frequency points by the number of points (10).
Table 16: Features extracted from sensor data to use when training machine learning
models
Feature Description
Points 1-10 y-value of data points in given cycle, course-grained to 10 points, giving 10
features per sensor
AUC Area under the curve for the given cycle
Max_Value Maximum y-value in given cycle
Min_Value Minimum y-value in given cycle
Average Mean y-value of all data points in the given cycle
P2P_Amplitude Peak to Peak Amplitude: Max cycle y-value – Min cycle y-value
MaxLoc Location on the x-axis of the maximum value in the given cycle
MinLoc Location on the x-axis of the minimum value in the given cycle
RMS Root mean square value of all data points in the cycle
MaxSum Value of largest sum of 300 contiguous points
MaxLoc Center of max 30% of data (largest sum of 300 points)
Frequency 1-10 Power spectrum between 0 and 6 Hz split into 10 bins, giving 10 features per
sensor
Centroid Location of centroid of power spectrum with respect to frequency

87
5.2.5 Regression Models
Due to challenges encountered when normalizing the EMG readings in SCI
patients, where no maximum exertion is possible, selecting the normalization method
that best corresponds with the amount of force exerted by the muscles was difficult.
Several normalization techniques were trialed, including normalization by subtracting the
baseline EMG reading before rocking started, using the peak-to-peak amplitude of the
EMG readings during rocking, and normalizing by dividing each reading by the
maximum reading recorded during rocking. Ultimately, training targets were based on
EMG readings which were normalized by subtracting the baseline reading from each data
point.
For training, data was segmented into a training data set and test datasets. First,
data from each participant was segmented in half, and the first half of the data from all
participants was assembled into a training dataset. The second half of the data for each
participant was used to test the trained regression model.
Two regression models were developed. The first was developed using multiple
linear regression in Prism 10 (GraphPad Software, San Diego, CA, USA). First,
predictors were standardized by scaling to have a mean of zero, and a standard deviation
of 1. Variance inflation factors (VIF) were calculated and were used along with a
correlation matrix to manually remove predictors with a high degree of
multicollinearity. Once all predictors had a VIF < 10, p-values of the remaining
predictors were used to manually eliminate predictors which contributed little to the
model. Multiple linear regression was then performed, and β values were produced for
each predictor. This

88
procedure was repeated for each muscle. A custom MATLAB script was then used to test
the models using testing data from each child.
Another regression model was also created, using the MATLAB regression
learner. To evaluate for the optimal training method, sample datasets were trained all
available methods including linear regression, regression trees, support vector machines,
Gaussian process regression, kernel approximation regression, and ensembles of trees.
Models were initially screened by comparing mean squared error (MSE) for sample
datasets. A custom MATLAB script (Appendix A) was used to train the model using
the ensembles of trees method, with the boosted trees option.
5.2.6 Neural Network Model Development
A nonlinear input-output time-delay neural network was created and trained in
MATLAB, using sensor data as the predictors and EMG data as the targets. As with the
data for the regression model, to standardize the length of a rocking cycle across subjects
and cycles, and to ensure that time delayed inputs would always be representative of the
same point in the rocking cycle relative to the target, data were interpolated to 1000 data
points per rocking cycle. To optimize the network’s parameters, several models were
trained, altering input delays and the number of layers.
EMG and sensor data from each subject was split into training, testing, and
validation datasets, with training data comprising the first 60% of the data, and testing
and validation data comprising the 20% immediately following the training data, and the
final 20% respectively. Since muscle activation, which provided the target data for
training the neural network in the form of EMG data, was driving the sensor output, the
sensor data was offset from the EMG data, so that the inputs used to predict a specific
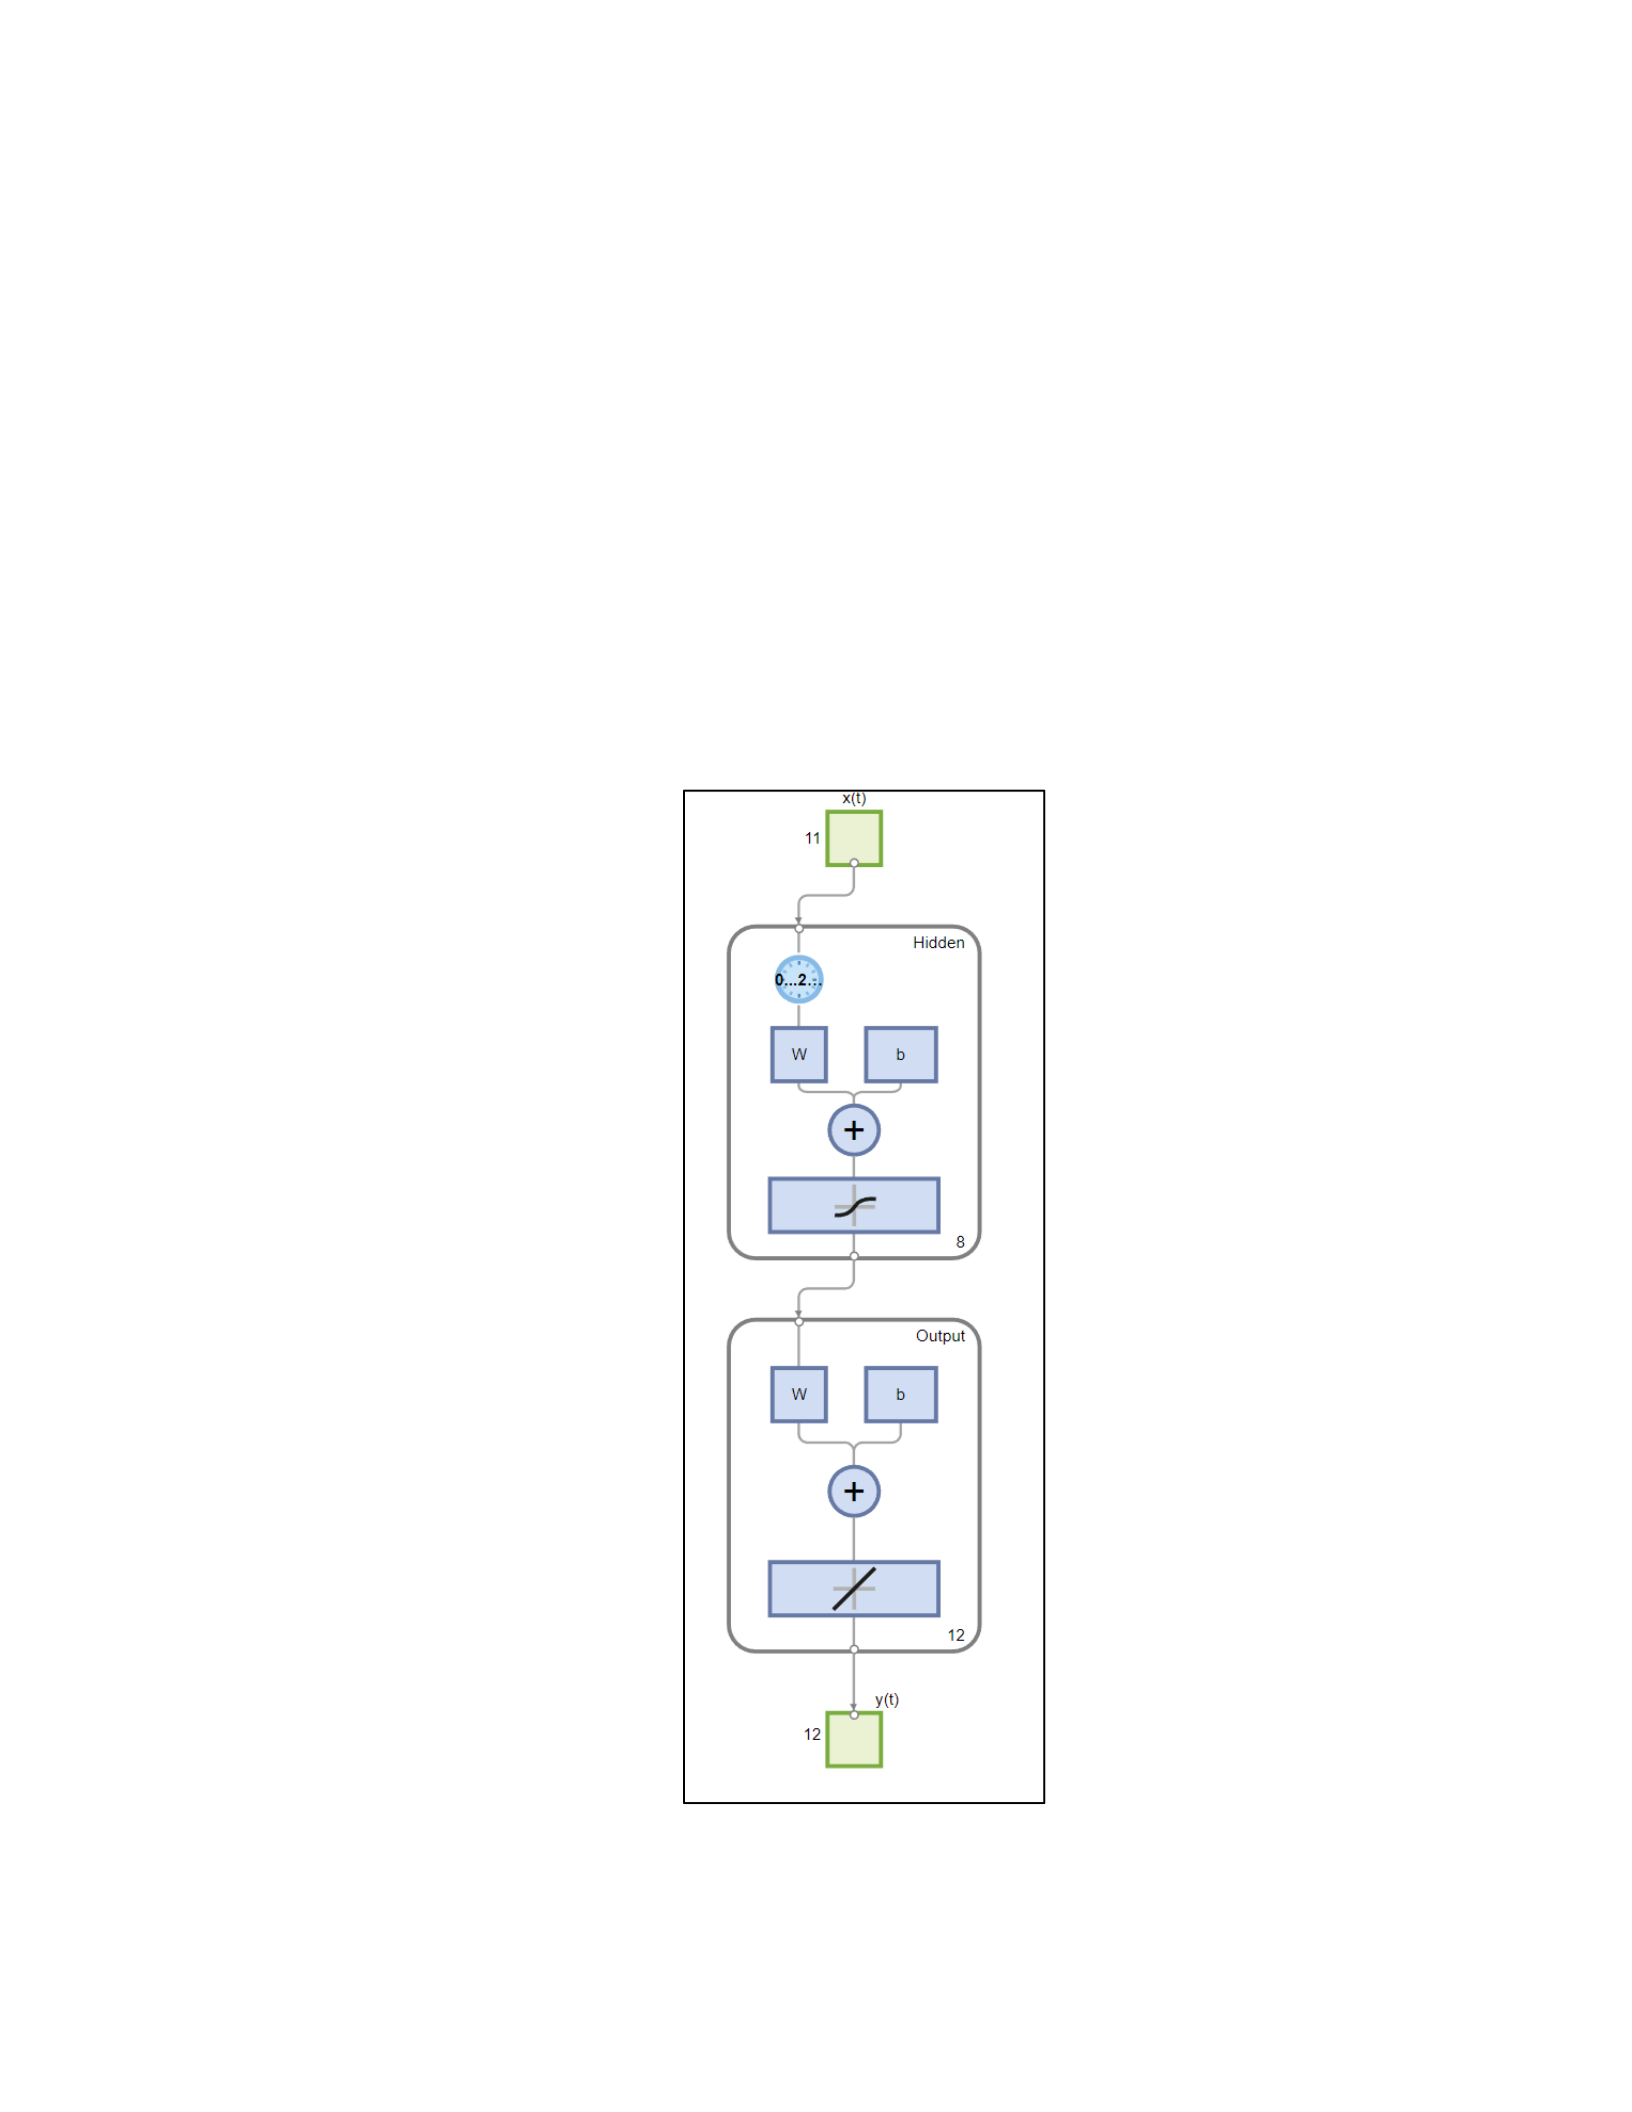
89
target value were taken from the rocking cycle immediately following the target as well
as the rocking cycle previous to the target time point.
The network was trained using Bayesian Regularization backpropagation, a
network training function that uses Levenberg-Marquardt optimization to update weight
and bias values. By minimizing a combination of squared errors and weights, it penalizes
large weights and produces a network that generalizes well [74, 75].
The network was set to 8 hidden layers, 11 inputs based on the 11 sensor values,
and 12 outputs for muscle activation targets as shown in Figure 21. Input delays were
Figure 21: Neural Network diagram with 11 inputs, 8 hidden layers, and 12 outputs

90
between 0 and 2000 with a step-size of 100, giving an array of 21 values for each input (1
at the same time point as the target, 10 from the previous cycle, and 10 from the
subsequent cycle). Maximum number of training epochs was set to 100, with a stop
condition of 10 consecutive validation failures. Separate models were trained for each
child, and trained models were tested using the prepared testing datasets.
5.2.7 Model Evaluation
The multiple linear regression model, ensemble regression model, and the NN
model performance were tested using the test dataset previously created. Several
measures of model performance were calculated based on the predictions produced by
the entire test dataset. These include R2, Mean Absolute Percentage Error (MAPE), Mean
Squared Error (MSE), Root Mean Squared Error (RMSE), Mean Absolute Error (MAE),
and Sum of Squares (SS) [76], which were calculated for each model and compiled into a
table for comparison.
To investigate the utility of the models in predicting muscle activation patterns in
individual children during rocking, the test data for each child in the SCI group was used
to predict muscle activation with each model. Correlation of the means of predictions
with targets for each muscle was calculated to evaluate how well the activation patterns
identified by the predictions matched the observed muscle activation. Many of the
datasets failed normality tests, so Spearman correlation analysis was selected, and results
were compiled into a table.

91
5.2.8 Evaluation of Sensor Data Correlations
Features were evaluated for correlation with muscle activity using the Minimum
Redundancy Maximum Relevance (MRMR) algorithm in the MATLAB regression
learner. For each muscle, the feature that was rated highest was tabulated and results
were compiled into a table showing the sensors that were most correlated with trunk,
arm, or leg muscle activity.
5.3 Results
5.3.1 Model Comparison
Table 17: Comparison of error for muscle activity prediction models
R Squared MAPE MSE
Multiple
Linear
Regression
Decision
Tree
Regression
Neural
Network
Multiple
Linear
Regression
Decision
Tree
Regression
Neural
Network
Multiple
Linear
Regression
Decision
Tree
Regression
Neural
Network
Cervical PS 0.000 0.226 0.402 229% 127% 59% 179.7 70.2 352.3
Thoracic PS 0.115 0.506 0.466 724% 309% 56% 583.4 79.3 169.5
Lumbar PS 0.006 0.411 0.441 738% 265% 72% 454.6 66.6 112.3
Pectorals 0.085 0.336 0.500 1996% 1459% 45% 502.8 64.2 106.2
Biceps 0.109 0.464 0.460 2641% 1394% 113% 1973.6 672.2 910.6
Triceps 0.246 0.434 0.444 751% 772% 87% 515.6 135.1 336.8
Rectus Abdominis 0.140 0.440 0.758 1359% 446% 58% 1218.6 84.1 67.1
Oblique 0.008 0.162 0.591 506% 206% 42% 115.8 38.4 28.9
Rectus Femoris 0.008 0.299 0.472 3335% 558% 61% 963.1 107.7 163.9
Hamstring 0.033 0.429 0.578 4082% 441% 56% 2908.2 73.0 96.5
Tibialis Anterior 0.007 0.261 0.584 7811% 1428% 66% 2200.5 234.8 242.8
Gastrocnemius 0.004 0.572 0.420 13809% 964% 81% 4176.1 90.4 189.4
R2 = R Squared; MAPE = Mean Absolute Percent Error; MSE = Mean Squared Error; PS = Paraspinals
Table 15 compares several measures of error in each of the models. R2 describes
the proportion of the variance in observed activation in the given muscle that is described
by each of the models. R2 values for successful regressions typically range between 0 and
1, with higher values indicating a more successful regression. MAPE quantifies error in
terms of percentages, making it suitable for comparing models with target data that has

92
been scaled differently, or when models have been tested on different data, as in the case
of the neural network and the regression models. Mean squared error tends to be more
sensitive to outliers than other measures of error and is the metric that is used by
MATLAB to evaluate model performance during training [76].
R2 and MAPE were the primary metrics used to compare models, due to their
ability to compare models with outputs that are scaled differently from each other. By
both these measures, the neural network outperformed both regression models, with the
decision tree regression receiving a higher R2 value than the neural network for only three
muscles (thoracic paraspinal, biceps, and gastrocnemius) and multiple linear regression
scoring worst in both measures for all muscles except the triceps, where it scored very
slightly (751% vs 775%) better than decision tree regression.
5.3.2 Muscle Activation Pattern Prediction
Spearman correlation analysis of muscle activation predictions is shown in Table
16. Multiple Linear Regression predictions were significantly correlated (p < .05) with
targets for four of the eleven children with SCI, while Decision Tree Regression
predictions were significantly correlated with targets for five children. Neural Network
predictions were significantly correlated with targets for all children.

93
Table 18: Spearman Correlation Analysis of Predictions for SCI Group
Participant
ID Multiple Linear Regression Decision Tree Regression Neural Network
P15 -0.161 CI (-0.683, 0.470) p = 0.619 0.371 CI (-0.276, 0.786) p = 0.237 0.937 CI (0.778, 0.983) p = <0.0001*
P21 0.112 CI (-0.508, 0.656) p = 0.733 0.727 CI (0.245, 0.921) p = 0.01* 0.958 CI (0.848, 0.989) p = <0.0001*
P23 0.587 CI (0.001, 0.873) p = 0.049*0.35 CI (-0.298, 0.777) p = 0.266 0.979 CI (0.947, 0.996) p = <0.0001*
P32 0.636 CI (-0.020, 0.868) p = 0.03*0.573 CI (-0.020 to 0.868) p = 0.055 0.993 CI (0.973, 0.998) p = <0.0001*
P34 0.294 CI (-0.622, 0.549) p = 0.354 -0.056 CI (-0.622, 0.549) p = 0.869 0.965 CI (0.872, 0.991) p = <0.0001*
P215 -0.133 CI (0.61, 0.968) p = 0.683 0.881 CI (0.61, 0.968) p = 0.0003* 0.895 CI (0.65, 0.972) p = <0.0001*
P187 0.045 CI (-0.583, 0.640) p = 0.903 0.445 CI (-0.230, 0.831) p = 0.173 0.748 CI (0.153, 0.919) p = 0.007*
P188 0.882 CI (0.585, 0.970) p = 0.0007*0.673 CI (0.102, 0.910) p = 0.028* 0.993 CI (0.963, 0.998) p = <0.0001*
P216 0.273 CI (-0.374, 0.741) p = 0.391 0.517 CI (-0.099, 0.847) p = 0.089 0.986 CI (0.947, 0.996) p = <0.0001*
P204 0.294 CI (-0.354, 0.751) p = 0.355 0.636 CI (0.079, 0.890) p = 0.03* 0.979 CI (0.973, 0.998) p = 0.001*
P217 0.764 CI (0.284 to 0.938) p = 0.0086*0.682 CI (0.119, 0.913) p = 0.025* 0.832 CI (0.324, 0.943) p = <0.0001*
Spearman r (95% Confidence interval) p-value of correlation between the mean muscle activation
predictions and targets for each child in the SCI group; *Significant (P < .05) correlation between
predictions and targets
Figure 22 compares predictions from each of the three models for one of the
participants with SCI (P188). For this example, which showed significant correlation for
all models, one can see that, although the distribution of predictions for a given muscle is
often different than that of the targets, the general muscle activation pattern is similar.
Thus, a therapist looking at these predictions would be able to get an idea of which
muscles were primarily being activated during rocking, even if the exact magnitude of
activation was uncertain.
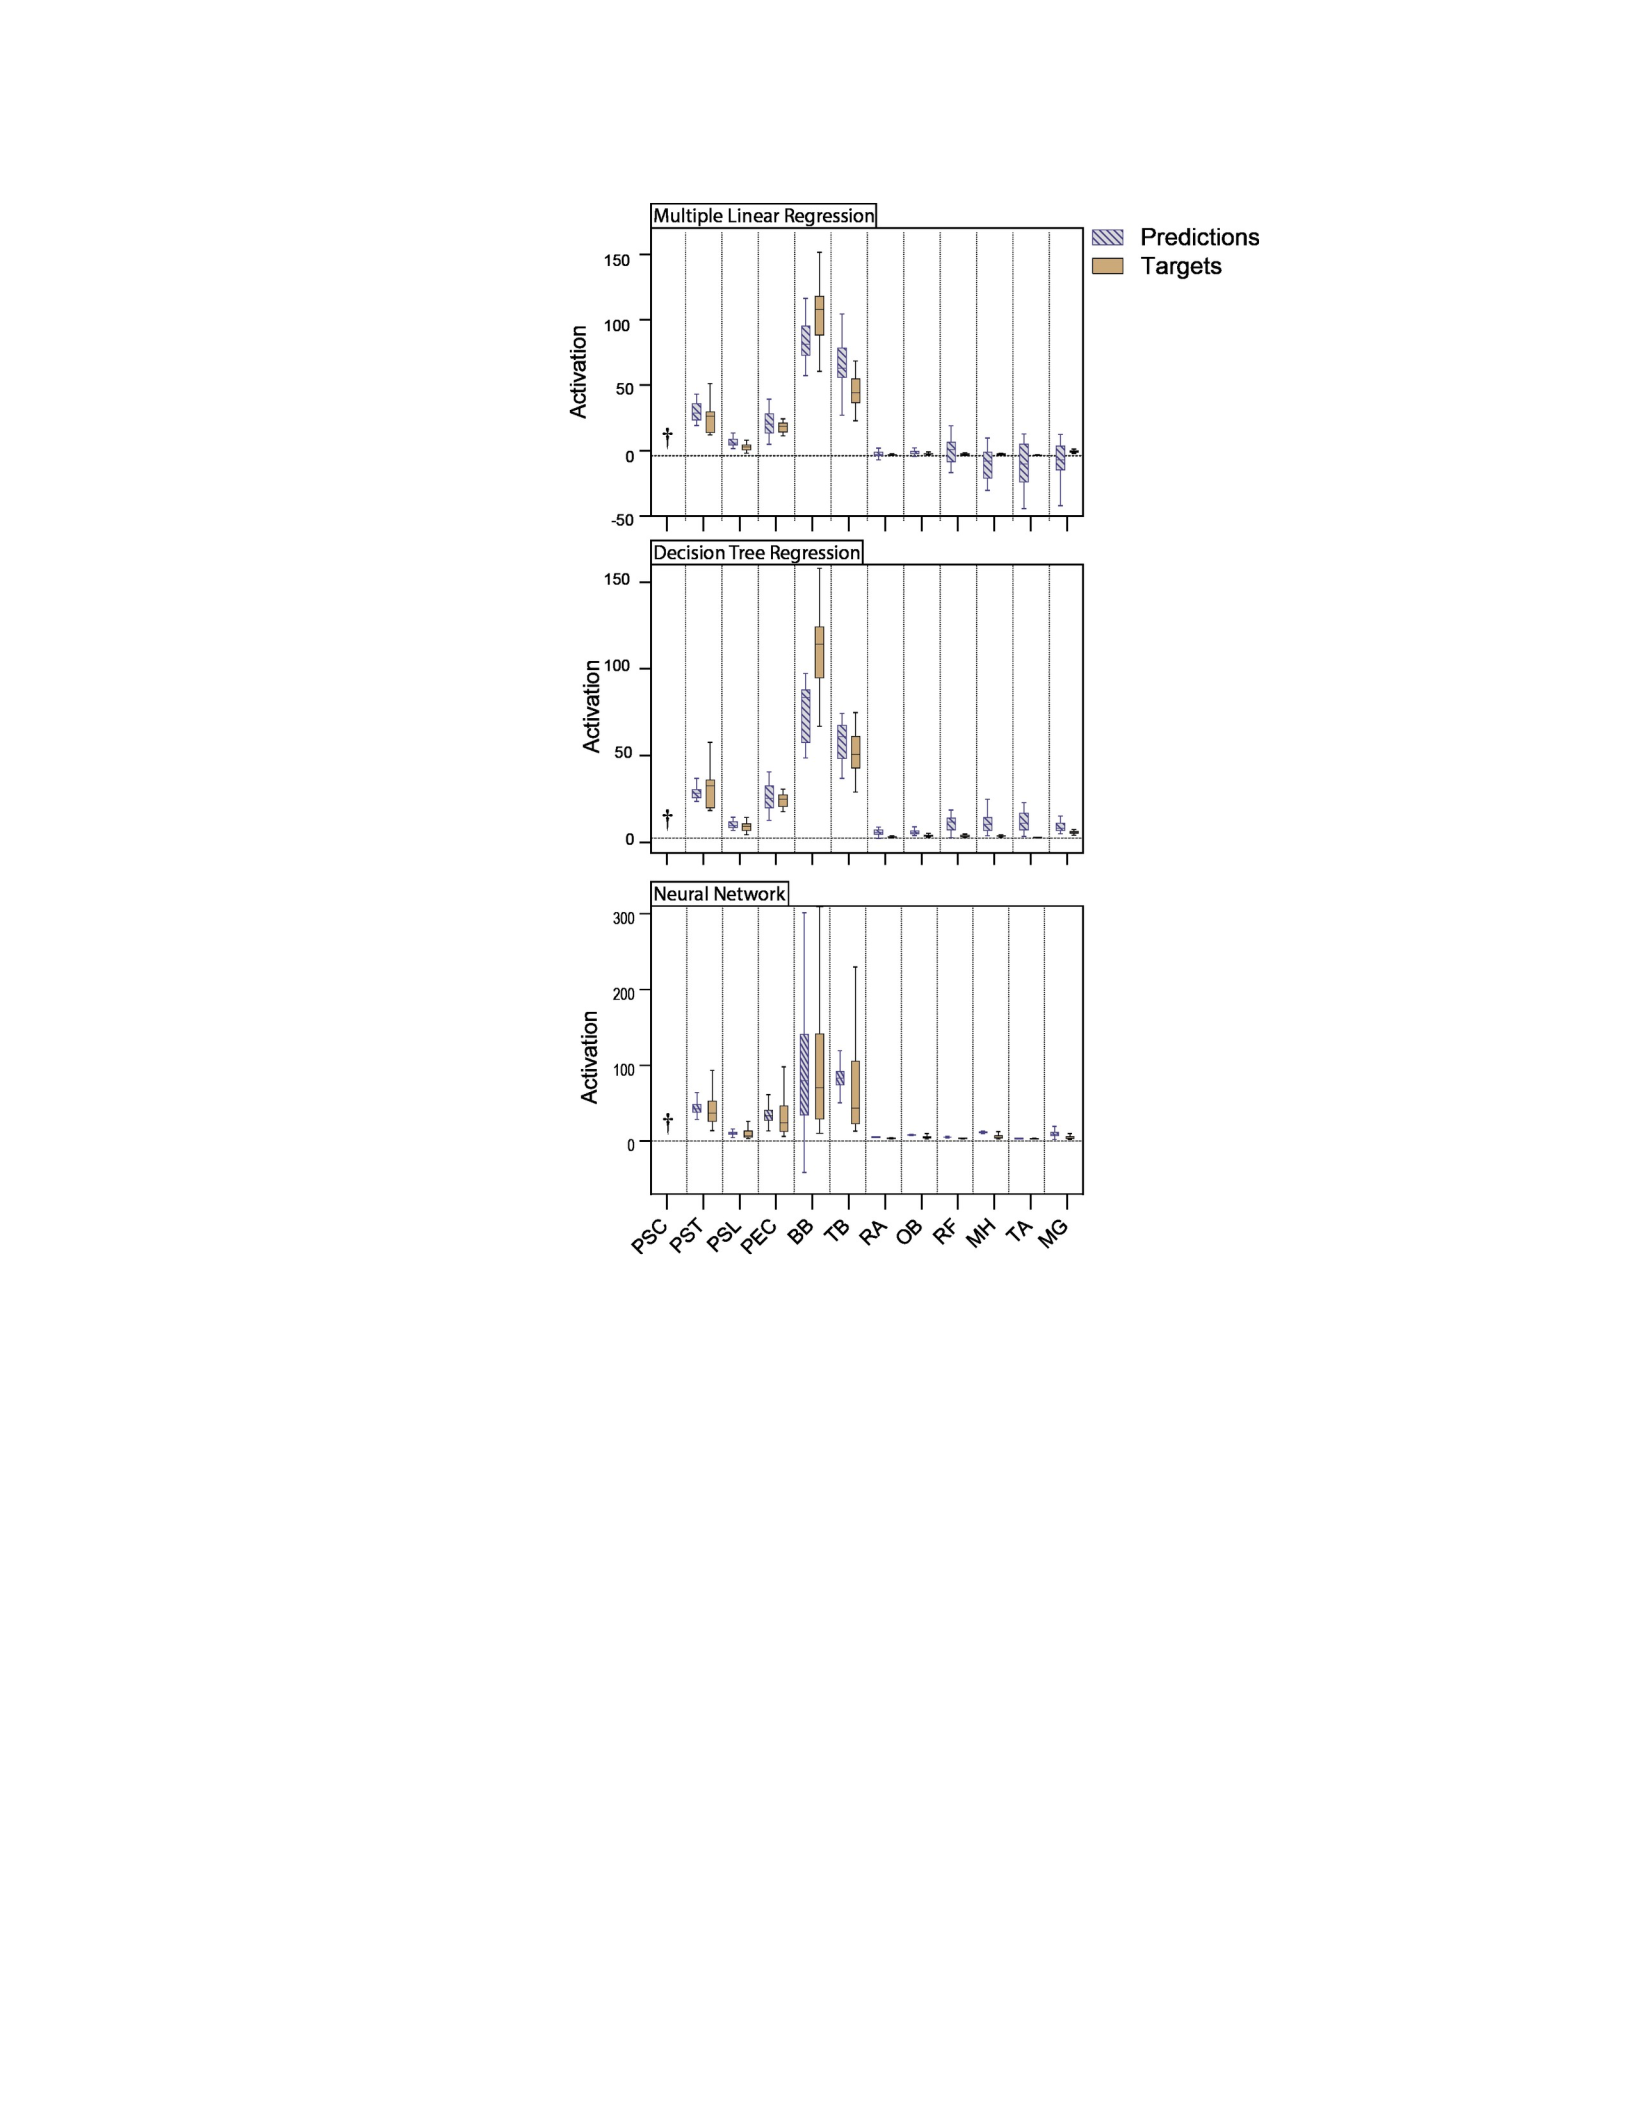
94
Figure 22: Example of muscle activation pattern predictions vs. target muscle
activations for one participant with SCI (P188). Note that y scale for Neural Network
predictions is different than for regression models due to differences in calculating
targets. Activation is expressed in µVRMS.
5.3.3 Sensor Correlation with Muscle Activity
MRMR analysis results are shown in Table 17. MRMR analysis revealed that the
strap data produced more highly relevant features (29) than any other sensor. However,
if all seat sensors are considered together, it surpasses the strap-based features with 39
95
highly relevant features. Strap features were highly relevant only for trunk and arm
muscles, with no highly relevant features related to leg muscle activity. Other sensors
showed a similar pattern of being more relevant to muscles they interacted more closely
with. The footrest produced features that were more relevant to leg muscles (6 for legs, 3
for trunk, 0 for arms). Seat sensors produced highly relevant features for muscles in all
domains with relatively balanced correlation to both upper and lower body muscles (19
for legs, 21 for upper body).
Table 19: Minimum Redundancy Maximum Relevance Analysis of correlation between
features derived from each sensor and muscle activity in trunk, arms, and legs
Sensor
Trunk
Extensors
Trunk
Flexors Arms
Legs
Extensors
Legs
Flexors Total
Strap 15 7 7 0 0 29
Left Arm 0 1 5 2 1 9
Right Arm 2 2 2 1 0 7
Seat 0 1 1 1 1 1 5
Seat 1 0 0 2 1 1 4
Seat 2 2 1 2 2 2 9
Seat 3 3 2 2 3 4 14
CoP 0 3 0 3 1 7
Footrest 2 1 0 3 3 9
Accelerometer 3 2 4 4 6 19
Position 2 0 4 0 1 7
Count of how many features based on each sensor were the most correlated
with different muscle groups; CoP = Center of Pressure
5.4 Discussion
5.4.1 Model Utility
There are two main metrics for evaluating whether the developed models are
useful to therapists. First, while exact determination of muscle activation at a given point
in time is not necessary, knowledge of the average activation of a given muscle relative
to other muscles during a rocking session would be useful in helping therapists determine
muscle use patterns, and to track changes in muscle use patterns over time. Correlation

96
analysis shows that the neural network performed better than either regression analysis,
with predictions significantly correlated to targets for all children.
Although correlation does not guarantee that the magnitude of each prediction is
close to the magnitude of the targets, Spearman correlation does show that the rank of the
corresponding predictions and targets are similar, and statistically significant correlation
shows that when ranked from most to least active, the order of predictions is similar to (if
not precisely the same as) the targets.
Second, models should at minimum detect whether a specific muscle is “turned
on” during rocking or whether it is inactive. With respect to this metric, the neural
network model performed well, accurately predicting very low activation (arbitrarily set
to < 5 µVRMS for purposes of this analysis) in 34 out of 41 cases, and only incorrectly
predicting low activation in two cases. The regression models, on the other hand, tended
to overestimate leg muscle activity for most children, while also underestimating activity
in those with significant leg muscle activation.
5.4.2 Sensor Relevance
In addition to the predictions produced by the models, the MRMR analysis
provided valuable information about the contribution of each sensor to predictions.
Importantly, sensor data was found to be most relevant to activity in muscles that they
interacted more closely with. For instance, force sensors in the footrest produced data that
was relevant to leg muscle activation, while sensors near the trunk (strap, armrest)
produced data more correlated with trunk muscle activation. This helps to reinforce the
conclusion that the sensor data contains information about muscle activation, and that the

97
machine learning models are using this to create their predictions, rather than simply
overfitting based on unrelated data. Knowledge of how sensors contribute to the models
for each muscle can also guide future sensor placement and feature selection decisions.
5.4.3 Limitations
The predictions made by these models are based on test data gathered in the same
session as the training data so, while the data used for testing had not been specifically
seen by the model during training, it was relatively similar in terms sensor data and EMG
target data. Thus, it is likely that at least some of the results are based on the model
learning to recognize the sensor data unique to a particular child and making predictions
consistent with muscle activation typical for that child. Until data can be collected across
several sessions in which there are differences in muscle activation patterns and in sensor
data collected it will be difficult to tell how well the model is able to detect changes in
muscle activation across time and across rocking sessions. Similarly, we cannot at this
point quantify how well this model would generalize to other subjects who had not had
the model trained on their data.
5.4.4 Future Work
There is need to collect additional data to assess the generalizability of the current
models across subjects and over time. These expanded datasets can be used to test the
accuracy of current models when applied to new data, and to facilitate their extending
their predictive capacity to a broader range of situations.

98
Current models produce data that is potentially useful to therapists, but a more in-
depth analysis to determine the level of accuracy and reliability required for predictive
models to be of practical use is needed. This will entail a systematic investigation to
ascertain the specific thresholds and criteria necessary to render predictions clinically
meaningful.
Future investigations should also expand on the work done on correlations of
different sensors with muscle activation to explore alternative types and locations for
sensor placement, such as the back of the seat, to enhance the accuracy and precision of
predictions.
To translate these findings for clinical use, it will be necessary to continue to
work with therapists to define the best measures to machine learning algorithms toward,
and to develop tools to provide the collected data to therapists in ways that are,
convenient, timely and useful.
5.5 Conclusion
This study demonstrates the potential of instrumented rocking chairs for
predicting muscle activation in pediatric SCI patients. Current models demonstrate that
machine learning techniques can be used to extract information about muscle activation
from force and motion sensors embedded in a rocking chair. While questions remain
about how well these results can scale across time and subjects, further research is
warranted to refine and validate these models for a broader population of pediatric SCI
patients. By exploring these avenues, future research can advance the efficacy and
applicability of predictive models in clinical settings.

99
CHAPTER 6
CONCLUSIONS AND FUTURE
DIRECTIONS
6.1 Research Objectives
Affectionately known as Rockin’Rehab, this project was structured to accomplish
four major objectives focused on the needs of children with spinal cord injury through the
development of a simple yet novel mechanism to activate trunk muscles.
The first project aim was to design and build a rocking chair that could be used by
children with SCI. The hope was that rocking would prove to be an accessible activity
that these children could do on their own regardless of their level of impairment, and that
in conjunction with other components of an ABT program, would augment the gains in
trunk control made through participation in locomotor training. Of primary importance
was to design and fabricate a rocking chair that would accomplish these goals in a safe,
enjoyable way.
The second project aim was to investigate how rocking in the rocking chair
affected muscle activation in children with SCI as compared to TD children. The
primary research question was whether muscles of interest (primarily trunk muscles, but
also muscles in arms and legs) would be activated during rocking. Another goal was to
describe both temporal muscle activation patterns and which muscles typically would be
used to drive rocking.
The third and fourth aims of the project were both centered around the use of
various sensors to instrument (sensorize) the rocking chair, which could be used to gather

100
data about the rocking experience that would be of use to therapists in the ABT program.
This would involve design and implementation of the sensor placement and data
collection systems, and the development of algorithms to detect muscle activity based on
the collected data.
6.2 Key Findings and Implications
The most important outcome of this study was the discovery that trunk muscles,
as well as muscles in the arms and legs, are activated by rocking. This significant finding
helped to achieve the second aim, which confirmed that rocking is a promising activity
for use in conjunction with a program of ABT.
The successful build of the rocking chair, and validation that it provides a safe,
enjoyable, and accessible activity for children with SCI was also an important outcome of
this research. The use of the QFD design method helped to ensure that the needs of both
the therapists and users were met and provides a solid reference point as further
developments and improvements to the rocking chair are implemented. The rocking chair
prototype was also found to be accessible and enjoyable to children with varying levels of
impairment, which helps to add confidence that children will use it.
The analysis of data collected by commercially available sensors embedded at
strategic locations in the chair to detect muscle activity was a novel idea and was the
most exploratory of the major objectives of this research. Although more work remains
to be done to fully develop these techniques for clinical use, the current results are
promising, and this technique may be applicable to other rehabilitation contexts.

101
6.3 Challenges and Limitations
Some limitations related to the design of the rocking chair were discovered during
rocking sessions with participants. Most of these were related to the ability of the rocking
chair to adjust and accommodate children of different sizes. While the chair enabled
children over a wide range of size to rock, some of the adjustments necessary to make
this possible disrupted other factors such as balance. This may in turn have influenced
muscle use patterns during rocking. Rethinking the methods of adjusting the chair in
ways that mitigate these interactions may be possible. For instance, instead of moving the
child in the seat to fit the distance to the footrest to the user’s leg length, the footrest
could be made to move backward and forward as well as up and down. Similarly,
physically adjusting the depth of the seat instead of changing its effective depth by
padding the backrest could address problems with fit, without changing the balance of
the seat.
Additionally, while fit was considered in setting up the rocking chair for the user,
it was not carefully characterized to investigate for its effects on muscle activation
patterns and its potential role as a confounding factor in the analyses performed. Data
that was collected about fit suggests that some factors (particularly balance) may have
had an effect on temporal muscle activation patterns, but without more precise data and a
larger sample size it is difficult to verify and quantify these effects.
Sensors used for sensing forces applied to the rocking chair were chosen for their
form factor which integrated easily into the rocking chair without interfering with its
operation. Some sensors, particularly the FSRs used in the seat and armrests, can suffer
from issues with hysteresis and drift. To some extent these issues are mitigated by the use

102
of standardization techniques used in machine learning and regression, where the data is
scaled to a mean of zero and an SD of 1. The time-dependent nature of hysteresis and
drift may, however, introduce noise into the data that isn’t completely removed by
standardization techniques, and complicate the attempts to glean meaningful information
about muscle activation from it.
Another challenge to training the machine learning models to predict muscle
activation was that all training data came from one relatively short rocking session, with
no major changes in rocking style or muscle use patterns over the course of the session.
This made it difficult to confirm that the models that were developed would generalize to
subjects whose data was not in the training dataset, or even to data taken from the same
subjects at subsequent rocking sessions. Until more data can be collected and models can
be refined, their reliability and utility will remain in question.
Finally, the temporal muscle activation patterns found for children with SCI are,
in some cases, likely to be an average of several different activation patterns rather than a
true representation of typical pattern for children with SCI. This may be due to children
with SCI possessing a wide variety of muscle activation patterns due to the need to
compensate for individually unique impairments. It is likely that instead of attempting to
define one typical pattern from children with SCI, the emphasis should be on defining the
patterns that are typical for TD children, and to study the ways that different impairments
alter muscle activation patterns to differ from what is typically seen.
6.4 Future Directions
Over the course of the project, several observations and suggestions for
improvements and additional features for the rocking chair were identified. Suggested

103
changes include items such as a larger footrest with straps to secure the feet, two or more
rocking chair models of different sizes, wheels to make transport of the chair easier, an
interlock to prevent chair rocking during transport, and other practical suggestions. These
adaptations should be examined to determine the need they are intended to meet, and
evaluated with for how well they meet the identified need in the same QFD manner from
the original chair build. Any features that fill an identified need should be implemented in
future versions of the rocking chair, or an alternative feature should be developed to meet
that need. Adult SCI patients may also benefit from the natural activity of rocking, and
additionally design parameters should be considered when developing for this population.
One goal of this project has been to move toward making rocking chairs available
for use in children’s homes, a hint towards the potential for commercialization of the
chair design. But this is also a reasonable proposition since it would allow patients to
further the gains from clinical LT in the home. To continue progress towards this goal,
the chair design should be refined to optimize for production of multiple units. In
addition, many of the suggested features discussed above are oriented towards making
the chair more useable at home, so they should be considered with any future redesigns.
Finally, any new designs will require further testing to ensure safety when used in the
home. A study to determine the minimum number of sensors that would still allow
tracking of chair use would also be appropriate.
To extend our knowledge of how use of rocking chairs in ABT contributes to the
progression of improved neuromuscular activation, studies involving long-term use of
rocking chairs in the home could be pursued. This kind of longitudinal research could

104
provide insight into whether rocking contributes to improvement in or retention of
intrinsic trunk control.
As mentioned previously, datasets representing more subjects, and representing
repeated data collections at different points in time would contribute to improved
training of machine learning models. Future research in this area could focus on creating
models that will generalize better, and on defining the reliability of models. In addition
to training with larger datasets, it would be helpful to work with therapists and other
clinicians to define the optimal balance between reliability of predictions, and specificity
of the predictions made.
Finally, other uses for the sensor data collected from the rocking chair could be
investigated. One example that is already in development is the incorporation of
advanced control mechanisms to use sensor input to assess the intent of the child. For
example, when a child needs additional help to maintain rocking, or alternatively needs
additional resistance so the rocking activity will continue to challenge them, mechanical
actuators working in concert with the sensor data could assist/resist rocking as
appropriate. Gamification of the rocking experience could also be explored using sensor
data to align the detection of activation of certain muscles and a reward system tied to
progress in the game.
6.5 Concluding Summary
In summary, this work has produced several valuable results. First, it has resulted
in a rocking chair that was designed and validated as a safe way for children with
impairments due to SCI to move independently, and to activate muscles. This has the
potential for use an integral component of a course of ABT therapy for children with SCI.

This study is also the first to investigate muscle activation patterns during
rocking, and to verify that rocking in a rocking chair can activate muscles throughout the
body for children with varying levels of impairment due to SCI. This sets the stage for
use of rocking chairs in the context of pediatric SCI, provides a base on which to build
further research into this topic and lays the groundwork for the development of new
techniques for quantifying muscle activation using common sensors combined with
powerful machine learning techniques. These tools should continue to be developed and
implemented in ways that will benefit children with SCI and, along with other therapies,
help them to improve their trunk control and their quality of life. Further research into
the benefits of rocking in this population should also continue to better define how these
tools can be used effectively, and to discover new applications where their benefit can be
realized.

