


INTRODUCTION THE SPREAD OF SEXUALLY TRANSMITTED
The spread of sexually transmitted infections (STIs) and the human immunodeficiency
virus (HIV) remains a significant public health concern in the United States (Centers for Disease
Control and Prevention [CDC], 2009). Young adults constitute one of the most vulnerable
groups to contract STIs and HIV, accounting for nearly half of new STI cases in the United States
(CDC, 2011a). Between 2005 and 2008 the CDC estimated that 3.9 million individuals ages 15-
24 were diagnosed with a STI, which does not include the millions of cases that go undiagnosed
each year (CDC, 2011a). Another 30,000 individuals, ages 13-24 are infected with HIV.
The high incidence of STIs among young adults may be attributed in large part to a lack
of effective sexual health education (Otto-Salaj, Reed, Brondino, Gore-Felton, Kelly, &
Stevenson, 2008). As a result, critics have called for more rigorous research to examine how to
improve current sexual health education programs (e.g., Airhihenbuwa & Obregon, 2000;
Corbett, Dickson-Gomez, Hilario, & Weeks, 2009). This study addresses this challenge by
examining one form of sexual health education, sexual negotiation training. More specifically, it
examines (a) the impact of sexual negotiation training as compared to standard sexual health
education on reducing sexual risk-taking among college students (b) whether intentions mediate
the relationship between sexual negotiation training and sexual risk reduction, and (c) whether or
not various relationship factors are linked with sexual risk outcomes among college students in
exclusive dating relationships who receive sexual health education.
The Current State of Sexual Health Education Programs
Despite the impressive number of sexual health education programs in the United States,
the ideas and principles commonly used to guide these programs have been challenged. Some
have criticized the use and efficiency of some of the most common theories (e.g., theory of
planned behavior) and models (e.g., health belief model) that guide sexual health education
programs (Freimuth, 1992; Yoder, 1997), noting that these programs are founded on principles
that emphasize individualism rather than the relational or multicontextual factors that impact
behavior (e.g., Kiene, Barta, Zelenski, & Cothran, 2005). For instance, Airhihenbuwa and
1

Obregon (2000) suggested that, “theories and models commonly used in health communication
and promotion clearly show that HIV/AIDS communication is based on the behavior and
decision-making process of so-called rational individuals who follow an established linear path
from awareness to attitude to actions” (p. 12). Proponents of relational based sexual health
education programs argue that individuals are not always rational in their decision-making and
that sex related decisions are often based on emotions, which are commonly linked to relational
factors.
Supporters of relational based programs also argue that sexual beliefs, decisions, and
practices originate from relational processes (Yoder, 1997). Supporting this view, some studies
show that relational processes regulate the ways in which individuals measure their state of
health and their health related behaviors (e.g., Umphrey & Sherblom, 2007; Williamson, Buston,
& Sweeting, 2009). In the context of sexual behaviors, one factor that impacts individuals’ use of
condoms is their ability to negotiate with their partner (Harvey et al., 2006).
Research that supports the link between dyadic interaction processes (i.e., communication
between partners about using condoms; Fox, 2009) and individuals’ sexual behaviors has
encouraged educators and community health officials to adopt sexual negotiation training
programs (e.g., Corbett et al., 2009). These programs provide skills based training that
emphasize sexual communication, negotiation, and decision-making (Hendriksen, Pettifor, Lee,
Coates, & Rees, 2007). Sexual communication strategies are used to encourage individuals to
communicate condom use requests with partners and to reinforce negotiation attempts. Implicit
in the training is the assumption that the negotiation strategies taught to individuals will help
them successfully communicate about safe sex practices with their partner. The training is meant
to help individuals engage in open dialogue about their trepidations, risk, and the barriers to
condom use. Research shows that sexual negotiation training can reduce risky sexual behavior
for heterosexual couples (Corbett et al., 2009), at-risk inner city women (e.g., DiClemente &
Wingwood, 1995), gay men (Crawford et al., 2006), and those with mental health illness
(OttoSalaj, Kelly, Stevenson, Hoffman, & Kalichman, 2001).
Despite the growing use of sexual negotiation training among various populations (e.g.,
Tschann, Flores, Groat, Deardorff, & Wibbelsman, 2010), no studies have examined the benefits
of sexual negotiation training among young adults in college. Also, despite the emphasis on
dyadic interactions (i.e., communication patterns), sexual negotiation training programs do not
2

clearly illustrate how important relationship factors (e.g., commitment level, relationship
satisfaction, trust) may be linked to individuals’ sexual decision-making and safe sex practices.
Not surprisingly, little data exists on how relationship factors are associated with education.
Further, there are no empirical studies that have looked at how relationship factors are linked to
sexual outcomes among college students receiving sexual health education. This study is the
first to examine whether or not relationship factors are linked to sexual outcomes among college
students receiving standard sexual health education and sexual negotiation training.
Sexual Health Education for College Students
For many, the college years provide “unprecedented personal freedom and multiple new
social experiences and relationships” (Gullette & Lyons, 2005, p. 47). However, during this time
of exploration many students put themselves at risk. Studies show that participation in at-risk
sexual behaviors among college students continues to grow (e.g., Synovitz, Wood, Gillan,
McKay, & Totten, 2008). About 86% of college students are sexually active, but only 35%
engage in consistent condom use (Lewis, Miglez-Burbano, & Malow, 2009). Also, more than
half of college students have reported engaging in at least one hookup encounter in the last year
(Owen, Rhoades, Stanley, & Fincham, 2010; Owen, Fincham, & Moore, 2011) and 23-49% have
engaged in sexual infidelity while in college (Vail-Smith, MacKenzie, & Knox, 2010; Negash,
Veldorale-Brogan, & Fincham, under review). Many college students also have misconceptions
about what constitutes safe sex (i.e., using condoms during vaginal sex only, using
hormonebased birth control, and having oral sex; Sadovszky & McKinney, 2002). These
findings, in part, may explain why those in their early 20’s are at greatest risk for contracting
STIs (CDC,
2011a).
The high incidence of STIs and HIV among young adults and the ubiquity of casual sex
among college students clearly suggest that sexual health education remains important in college.
Despite this, the vast majority of sexual health education is provided to adolescents prior to
leaving high school, and there is no federal or state mandate to provide sexual health education to
college students (King, 2011). Findings from a preliminary study at The Florida State University
indicated that it had been at minimum 3-4 years since an estimated 44% of the 839 college
participants sampled (the vast majority of which were freshman and sophomores) had received
sexual health training (Negash, 2011). Given the lack of sexual health training on college
campuses and the lack of efficacy research regarding the use of sexual health education with
3

college students, it is important to examine sexual health education in this population. The
present study addressed this deficit.
Sexual Health Risk in Exclusive Dating Relationships
It is not uncommon for young adults to move from one exclusive relationship to another
in a short duration (Kelley, Borawski, Flocke, & Keen, 2003). Many also go untested for STIs or
HIV prior to beginning a sexual relationship. For these reasons, young adults are at risk of
unknowingly transmitting a STI or HIV to their exclusive partner (Kelley et al., 2003;
Rosenberg, Gurvey, Alder, Dunlop, & Jonathan, 1999). Despite this risk, considerable research
has found that in mutually monogamous relationships between partners, it is reasonable, and
even expected, that couples engage in sexual activity without the regular use of condoms (e.g.,
Wiemann et al., 2009; Warren, Harvey, & Agnew, 2010). For instance, a recent study by Lewis,
Keysen, Rees, and Woods (2010) showed that only an estimated 52% of college students in their
sample (n = 623), the majority of whom were in a monogamous relationship, used a condom
during their most recent sexual encounter (i.e., coitus). About half of participants from the study
also reported not using a condom the first time they engaged in coitus with their current partner.
Symptomatology. Many STIs are asymptomatic, making them difficult to detect by both
carriers and their sexual partners (Da Ros & Schmitt, 2008; Todd, Haase, & Stoner, 2001). For
instance, the majority of genital herpes infections are transmitted by persons who are either
asymptomatic but aware that they are infected, or asymptomatic and unaware that they are
infected (CDC, 2011a). Also, the CDC (2009) found that individuals who are HIV-positive, but
unaware of their status (an estimated 54-70% of all HIV-positive cases) are considerably more
likely to engage in risky sexual behavior and disproportionately more likely to infect sexual
partners, as compared to those individuals who are aware of their HIV-positive status. Although
asymptomatic infections are diagnosed through testing, many reasons have been identified for
why individuals do not get tested regularly. Individuals typically lack awareness about STIs and
HIV, are concerned about being stigmatized by society, and do not identify themselves as at-risk.
Consequently, these barriers place individuals at greater risk of infecting others.
Infidelity. Many individuals in exclusive relationships do not use condoms with primary
partners in order to reduce suspicion about infidelity (Duncan et al., 2002). In a study by Choi,
Catania, and Dolcini (1994), 60% of individuals who reported committing infidelity did not use
condoms with either their primary or secondary partner. The same study found that an estimated
20-25% reported intermittently using condoms with either partner. More recently, Brady,
4

Tschann, Ellen, and Flores (2009) found that individuals who were committed were less likely to
take proper precaution to protect their partner from contracting STIs. Many women in particular
put themselves at greater risk for HIV infection by maintaining an illusion of fidelity within their
relationship (Sobo, 1995). The nature of so called ‘monogamous’ relationships, the lack of STI
and HIV testing, in combination with the fact that many STIs are asymptomatic, demonstrates
why rates of risky sexual behavior are higher among individuals in exclusive dating
relationships, as compared to those in casual relationships (e.g., Parks, Hsieh, Collins,
LevonyanRadloff, & King, 2009).
Relational Factors that are Associated with Sexual Health
Maintaining intimacy. Relationship factors play a vital role in the use of condoms in
exclusive dating relationships. For instance, findings suggest that individuals assess risk and
condom use based on their thoughts and feelings regarding their current interpersonal
relationship, rather than their partner’s past sexual history (Civic, 2000; Corbett et al., 2009).
Researchers have also found that those in an exclusive relationship weigh the perceived risk of
negotiating safe sex practices with their partner against the potential implications for their
relationship (Arifi, 1999; Umphrey & Sherblom, 2007). For many, condom use is inconsistent
with establishing and maintaining relationships, and sustaining stable and loving relationships
supersedes individuals’ health concerns (e.g., Corbett et al., 2009; McAlister, Pachana, &
Jackson 2005). Afifi (1999) found that condom use within relationships threatened individuals’
ability to maintain positive identities and close relationships. Similarly, Marston and King
(2006) found that couples hesitated to or refrained from talking about safe sex practices for fear
that raising the possibility of risk may hurt their partner’s feelings or create emotional or physical
distance between them.
A similar, yet more recent study by Corbett et al. (2009) also found that individuals
reduced their condom use as an attempt to find and maintain exclusive relationships. The same
study called for sexual health education programs that recognize the importance of love and
intimacy by those at greatest risk of infection. Supporting this view, Rehman et al. (2011) found
that individuals who reported having overall better relationships were more likely to avoid
behaviors that threatened their relationships.
A considerable number of relationship barriers to condom use have been identified,
including communication, trust, relationship satisfaction, and commitment (e.g., Brady et al.,
2009; Castaneda, 2000; Manning, Flanigan, Giordano, & Longmore, 2009). These relationship
5

factors have all been identified as components of intimacy. Intimacy is defined as, “a quality of a
relationship in which the individuals must have reciprocal feelings of trust and emotional
closeness toward each other and are able to openly communicate thoughts and feelings with each
other” (Timmerman, 1991, p.19). Intimate relationships are also characterized as “close,
committed, interdependent, and durable bonds” (Abate & Cusinato, 2012, p. 440). Thus, rather
than identify intimacy as a relationship factor in this study I examined its various components
(e.g., communication, trust, relationship satisfaction, and commitment). Additionally, with the
exception of research linking communication with safe sexual health education and practice (e.g.,
Corbett et al., 2009), little research has examined how the relationship factors stated above are
associated with safe sex outcomes among individuals in exclusive relationships who receive
sexual health education.
Communication. Miscommunication and discomfort talking about condom use create
barriers for safe sex (e.g., Adimora & Schoenbach, 2002; Fox, 2009; Otto-Salaj et al., 2008).
Despite the positive link between safe sex practices and detailed sexual communication (e.g.,
DiIorio, Dudley, Lehr, & Soet, 2000) couples have varied levels of comfort when engaging in
sexual communication with their partner (e.g., Noar, Morokoff, & Redding, 2002). Safe sex
discussions that do occur between partners can be embarrassing and may lead some partners to
avoid asking and answering important safe sex questions (Cline, Johnson, & Freeman, 1992).
Individuals who lack knowledge about their partner’s sexual history (PSH) are also at
increased risk of acquiring a STI (Drumright, Gorbach, & Holmes, 2004). Despite this, the
degree and depth of discussion regarding sexual histories varies among couples in exclusive
relationships. Many fear that their questions may evoke negative emotions, such as
embarrassment or discomfort. In a study by Bolton (2009), participants reported that a possible
discussion with their partner regarding sexual histories would evoke feelings of awkwardness
and jealousy. In reference to discussing sexual histories, one participant said, “I don’t want to
because I am aware of how it would make me feel. That’s why I sort of don’t want to know” (p.
27). One’s knowledge about their PSH also informs their perceived sexual health risk and is
linked to their sexual decision-making (e.g., Drumright et al., 2004). Thus, given the link
between discussing sexual histories, decision-making, and actual health outcomes (Drumright et
al., 2004), it is important to examine the extent to which receiving sexual health education
impacts individuals’ knowledge about their PSH.
6

Trust. Condom use is linked with trust (Hirsch, Higgins, Bently, & Nathanson, 2002;
Montgomery et al., 2008). Requesting that condoms be used within an exclusive relationship
may imply that one does not trust their partner to keep them safe from infection or to be
monogamous (Duncan et al., 2002; Hirsch et al., 2002; Montgomery et al., 2008). More recently,
Brady et al. (2009) found that trust was independently linked to consistent condom use among
young adults in exclusive dating relationships. Similarly, Williamson et al. (2009) found that
despite not knowing their own STI status or their PSH, the vast majority of individuals in their
sample stopped using condoms once they perceived that they could trust their primary partner.
Commitment. Commitment is linked with decreased condom use (Casteneda, 2000;
Civic, 1999; Mnyika et al., 1997). Harvey et al. (2006) and Tucker, Elliott, Wenzel, and
Hambarsoomian (2007) found that frequency of condom use was directly linked to individuals’
relationship commitment. Similarly, Umphrey and Sherblom (2007) found that individuals in
relationships with low commitment were less likely to perceive the request for condom use as a
threat to their relationship.
Relationship satisfaction. Condom use has also been linked to relationship satisfaction
(Impett, Breines, & Strachman, 2010; Manning et al., 2009; Woodrome, Zimet, Orr, &
Fortenberry, 2006). Pilkington, Kern, and Indest (1994) found that individuals who reported
feeling more positive about their partner and relationship were less likely to be concerned about
contracting a STI or HIV and less likely to report that their condom use stemmed from a fear of
contracting STIs or HIV, as compared to those who felt less positive about their partner or
relationship. In another study, Soler et al. (2000) found that those who reported greater
satisfaction with their relationship were almost eight times less likely to use condoms
consistently, as compared to those who reported having some fear of HIV transmission.
More recently, Manning et al. (2009) found that positive relationship qualities (e.g., love,
enmeshment) were negatively linked with consistent condom use for both men and women.
Although evidence for the association between sexual risk behaviors and relationship factors
(i.e., trust, commitment, relationship satisfaction, and communication) exists, these associations
are understudied among college students in exclusive relationships and, to the best of this
author’s knowledge, have never been examined among college students receiving college-based
sexual health education.
7

Theoretical Perspective
Theory of planned behavior. Despite the criticism mentioned above about the use of the
theory of planned behavior (TPB) to guide sexual health education programming from a
relational perspective, the theory has been extensively and successfully used to predict condom
use in developed countries (Albarracin, Johnson, Fishbein, & Muellerleile, 2001). It has also
been widely used to develop STI and HIV prevention curricula (e.g., Albarracin et al., 2001;
Sheeran & Orbell, 1999). Thus, in the current study it is used to provide a framework for
examining the relationship between sexual health education programs and sexual risk reduction
among college students.
An expectancy-value model is used to predict individuals’ attitudes toward various
outcomes, and proposes that behaviors are a function of expectations and evaluations (Glanz,
Rimer, and Lewis, 2002). Accordingly, the TPB, which is an extension of the theory of reasoned
action (TRA; Fishbein & Ajzen, 1975), is a commonly applied expectancy-value model used to
link attitudes with behaviors. More specifically, the TPB is used to predict and assess a variety
of health behaviors, including substance use (Kam, Matsunaga, Hecht, & Ndiaye, 2009), physical
activities (Andrews, Silk, & Eneli, 2010), and sexual activities (Mausbach, Semple,
Strathdee, & Patterson, 2009). As shown in Figure 1, the TPB posits that intentions are the
proximal determinant of behavior, and that intentions are, in turn, formed by individuals’
attitudes, subjective norms, and their perceived control over a behavior (Ajzen, 1991).
According to the theory, the stronger the intention to engage in a behavior, the more likely one is
to execute said behavior.
In the context of sexual health, the theory proposes that as opposed to those who have
little or no intent to use condoms, those with greater intent are more likely to actually engage in
condom use. The intention to use condoms derives from individuals’ existing attitudes (e.g.,
whether or not they enjoy wearing condoms), subjective norms (e.g., perceived social pressure to
use condoms), and their perception of control over their use of condoms (e.g., constraints or
barriers to condom use; Albarracin et al., 2001). Consistent with the tenets posited in the TPB,
sexual negotiation training implements strategies to change individuals’ attitudes about condom
use. The training also attempts to alter individuals’ perception of what they perceive may be
normal sexual behavior (i.e., change their subjective norm), by illustrating realistic scenarios that
show other young adults negotiating condom use. In turn, this may also reduce the relational
pressure individuals feel to not use condoms. In accordance with another component of the TPB
8

(i.e., perceived behavioral control) sexual negotiation is also used to improve individuals’ sense
of control over their ability to use condoms, by illustrating how to apply condoms and bring up
condom use conversations. Consistencies between the components of the TPB and the sexual
negotiation training provided in this study suggest that theory may provide a useful framework
for understanding changes in condom use among college students who receive sexual negotiation
training.
Support for the link between receiving sexual health education and intentions for condom
use also exists (e.g., Bryan, Kagee, & Broaddus, 2006; Fisher & Fisher 2002). Despite this, the
present study is the first to examine whether or not condom use intentions mediate the
relationship between the treatment and condom use. It was also the first study to examine
whether intentions to gain information about a PSH mediate the relationship between the
treatment and condom use.
Investment model. The investment model (Rusbult, 1980, 1983) may offer theoretical
cohesion to some previous findings about safe sex practices among individuals in dating
relationships. The model, which is an extension of interdependence theory (Thibaut & Kelley,
1959), suggests that the driving force within relationships is commitment. Individuals’
commitment to their partner is based on three key elements, including satisfaction, investments,
and alternative quality. Satisfaction is based on the outcomes an individual receives from their
relationship and is positively related to commitment. Investments, which are also positively
related to commitment, represent the things an individual stands to lose if their relationship
dissolved. Alternative quality is also negatively related to commitment and represents the
outcomes an individual would expect from their desired alternative. Overall, the investment
model maintains that highly satisfied and invested individuals, who have fewer desirable
alternative options, are more likely to be concerned about the well-being of their partner and less
likely to engage in behaviors that may jeopardize their relationship (e.g., Drigotas, Safstrom, &
Gentilia, 1999; Van Lange, Agnew, Harinck, & Steemers 1997). Said differently, they are more
likely to weigh the ramifications that their behaviors may have on their partner and relationship.
As stated earlier, research shows that individuals perceive condom use and discussions
about past sexual history to be a threat to their relationship (Bolton, 2009; Rehman et al. 2011).
Similarly, the investment model maintains that more satisfied and invested individuals are less
likely to engage in behaviors that may harm the stability of their romantic relationships. Since
the model does not delineate between behaviors that are considered harmful, it is fair to assume
9

that safe sex may fall into the category of being harmful to one’s relationship. Thus, findings
from previous research negatively linking relationship quality with safe sex practices among
those in exclusive relationships (e.g., Castaneda, 2000; Manning et al., 2009) show support for
the investment model (Umphrey & Sherblom, 2007).
For the purpose of this study, the investment model perspective, in combination with
findings from studies that show that individuals in exclusive dating relationships are at greater
sexual risk, offer a useful framework for examining to what extent relationship factors are linked
to sexual risk reduction outcomes among young adults receiving sexual health training.
Subsequently, in accordance with previous research and the investment model I expect that
despite receiving sexual health education, individuals in overall better relationships will engage
in more risky sexual behaviors.
Purpose of the Study
The purpose of this study was threefold. The first purpose was to evaluate the impact of
sexual negotiation training as compared to standard health education on reducing sexual
risktaking among young adult college students. Secondly, I tested for potential mediators
between the conditions and sexual risk reduction outcomes. The third objective was to examine
whether or not relationship factors were associated with sexual risk outcomes among college
students in exclusive dating relationships. Since a “single, summative” assessment makes it
challenging to accurately measure changes in student outcomes (Olds, 2004, p. 162), the
objectives stated above were examined using pre- and post-test data.
Research Questions
Specifically, the questions posed included the following:
1. Are sexual negotiation programs useful at improving safe sex practices (i.e.,
increasing condom use, knowledge about a PSH, and condom use self-efficacy)
among college students?
2. Do condom use intentions mediate the link between condition and post-test
condom use?
3. Do intentions to be informed about a PSH mediate the link between condition and
post-test knowledge about a PSH?
4. Independent of condition, to what extent are relationship factors (i.e., relationship
satisfaction, trust, commitment, and communication) linked to condom use at
post-test among college students in exclusive dating relationships?
10

5. Independent of condition, to what extent are relationship factors (i.e., relationship
satisfaction, trust, commitment, and communication) linked to knowledge about a
PSH at post-test among college students in exclusive dating relationships?
6. Independent of condition, to what extent are relationship factors (i.e., relationship
satisfaction, trust, commitment, and communication) linked to condom use
selfefficacy at post-test among college students in exclusive dating relationships?
Hypotheses
1. It is predicted that participants in the treatment group will be more likely to (a) engage in
condom use, (b) have increased knowledge about their PSH, and (c) increase their condom use
self-efficacy at post-test as compared to those in the comparison group
(RQ1).
2. It is predicted that participants’ (a) condom use intentions mediate the relationship
between condition and condom use at post-test, and (b) intentions to be informed about a
PSH mediate the relationship between condition and knowledge about a PSH at post-test
(RQ2 and RQ3, respectively).
3. Independent of condition, it is expected that (a) relationship satisfaction, (b) trust, (c)
commitment, and (d) communication will be linked to condom use at post-test among
those in exclusive relationships (RQ3).
4. Independent of condition, it is expected that (a) relationship satisfaction, (b) trust, (c)
commitment, and (d) communication will be linked to knowledge about a PSH at post
test among those in exclusive relationships (RQ4).
5. Independent of condition, it is expected that (a) relationship satisfaction, (b) trust, (c)
commitment, and (d) communication will be linked to condom use self-efficacy at post
test among those in exclusive relationships (RQ5).
CHAPTER TWO
METHOD
Participants
Participants included 271 undergraduate students (226 women and 45 men) from a
Southeastern university who agreed to participate in exchange for course credit. Of those who
initially participated in the baseline study 243 completed the follow up (90%). However, data
11

were analyzed for those participants who met the inclusion criteria (n = 183). To be included in
the analyses participants were required to be (1) between 18-30 years of age, (2) complete a pre-
and post-test survey, and (3) be sexually active (see CONSORT diagram, Figure 2). Articles
from the CDC have identified young adults as those individuals aged 18-30 (Freedman, Nelson,
& Feldman, 2012). Thus, the same age range was used in the inclusion criteria for young adults
in this study. Also, to meet the inclusion criteria participants were not permitted to be in an
exclusive relationship with another participant in the study. Further, to be included in analyses
used to test hypotheses 3-5 (n =108) participants were required to be in a committed dating
relationship for at least 2 months and be in the same relationship over the course of the 1-month
study. Most participants were between 18 and 25 years of age (96.2%) and a small minority
were between 25-30 years of age (3.8%). The majority of participants were non-Hispanic White
(68%), 12% were African American, 17% were Hispanic, 2% were Asian/Pacific Islander, and
1% reported as Other. Descriptive statistics for the sample are shown in Table 2.
Procedure
The present study was a randomized controlled experiment, conducted in a laboratory
setting, and approved by The Florida State University Institutional Review Board (IRB; see
Appendix A). Participant consent and study procedures were carried out in accordance with the
IRB guidelines. All facilitators received training designed to provide information and skills
related to the specific intervention to encourage and ensure implementation fidelity. More
specifically, facilitators used a standardized procedure guide developed for the study that
outlined key points to cover and activities to perform. Additionally, the lead researcher discreetly
monitored facilitators and gave them cues to ensure fidelity to the time allotted for each activity.
Undergraduate students from a social science department were invited to participate in the
laboratory experiment almost two weeks before the study began. Prior to signing up students
were informed that they would be participating in a sexual health education study. Facilitators,
who did not know the participants, allocated participants into the treatment and comparison
group by flipping a coin each morning during the week of the experiment. Upon arriving at the
laboratory students were directed into particular rooms (based on whether they were in the
treatment or comparison group) and instructed to read and complete informed consent forms.
They were then given instructions about the task and encouraged to contact the on-site facilitator
if they experienced any challenges with the task.
12

At pre-test all study participants completed baseline measures. Baseline measures were
used to assess each participant’s condom use, knowledge about a PSH, barriers to condom use,
condom use self-efficacy, condom use intentions, intentions to gain knowledge about PSH,
relationship satisfaction, trust, commitment, communication, hookup frequency, and sexual
health history. Questions were administered and collected through the SurveyMonkey portal, a
secure online survey website. Subsequently, participants read through a 15-minute PowerPoint
presentation on STIs HIV/AIDS, and safe sex practices. Students were then randomly assigned to
either an intervention group where they watched a 19-minute sexual negotiation video (provided
by The Diffusion of Effective Behavioral Interventions project) or to a comparison group (e.g., to
complete a 10-15 minute writing assignment where they wrote about what they learned from the
standard sexual health education PowerPoint presentation). All participants were contacted
through their student email account one month after the initial experiment was conducted and
assessed using the same measures as baseline (also administered and collected through the
SurveyMonkey portal).
Intervention condition: Sexual negotiation training. Participants assigned to the
intervention group also completed a brief 20 minute writing task where they were asked to
identify (e.g., their own objections to using condoms and how information from the video could
be used to address their barriers to condom use; identify different condom negotiation strategies
using scenarios from the negotiation video; common excuses their partner might state for not
wanting to use condoms and role-play different condom negotiation strategies that may be used
to successfully and more comfortably challenge their excuses; identify how to put condoms on,
how and when to remove them, and how to dispose of a used condom). For instance, participants
were asked, “What are some clever things you can say when negotiating condom use with a
partner?” Participants in the intervention were also given the following instructions prior to
watching the video, “You have been assigned to watch a short training video about safe sex.
If at anytime you become uncomfortable with the content you may ask to stop the video. Such
honesty will not count against your receiving course credit.”
Comparison condition: Standard sexual health education. Participants in the
comparison condition received standard sexual health education. This comprised reading
through a 15-minute PowerPoint about STIs, HIV/AIDS and safe sex practices. After watching
this videotape they were given the following instructions prior to beginning the writing task,
“You have been assigned to reflect on the sexual health video by sharing information about what
13

you learned and what you thought about the information presented.” They then spent 10-15
minutes writing about what they learned.
Measures
Demographics. Demographic questions were used at pre-test to assess age,
race/ethnicity, relationship status, gender, and sexual orientation. Participants’ relationship status
was assessed again at post-test (i.e., “Have you ended a romantic relationship since you
completed the last survey for this study?” “Have you started a new romantic relationship since
you completed the last survey for this study?”). Responses were coded 0 = no and 1 = yes. A
dichotomous variable was constructed to test for those whose relationship continued (0 = in same
relationship from pre- to post-test) and those whose relationship ended (1 = no longer in the same
relationship from pre- to post-test). Participants who maintained the same relationship from pre-
to post-test were included in the analysis pertaining to those in exclusive relationships.
Sexual activity. To assess sexual activity among those in exclusive dating relationships,
at pre-test participants were asked, “Thinking of your current relationship, during the past two
months: Have you engaged in vaginal intercourse?” Participants were also asked similar
questions pertaining to their oral and anal sexual behavior. Responses were coded 0 = no and 1
= yes. Participants that were not in an exclusive dating relationship were asked to respond to the
same questions, but in the context of their last penetrative sexual encounter (i.e., “Please answer
the following series of questions about your relationship with your current exclusive romantic
partner. If you are not currently in an exclusive relationship answer the following with regards to
your most recent hookup partner”).
Condom use. To assess condom use participants were asked about their condom use
practices at pre-test using two items (i.e., “When was the last time you had sex with your partner
without using a condom?” and “How often do you use condoms with your partner?”).
Participants’ condom use was reassessed again one month later using the same set of questions
(i.e., “In the last month have you had sex with your partner without using a condom?”).
Responses for the questions were on a 6-point scale ranging from 1 = never to 6 = always.
Responses were summed to form a composite score and could range from 2 to 12 (pre-test, M =
6.88, SD = 3.50; post-test, M = 7.42, SD = 4.06) with higher scores indicating greater condom
use. These items demonstrated adequate reliability and had a Cronbach alpha of 0.86 at pre-test
and 0.97 at post-test.
14

Condom use barriers. The motivational barriers subscale from the Condom Use Barriers
Scale (CBS; St. Lawrence at al., 1999) was used to assess for factors that are perceived to inhibit
or reduce condom use. The six items were answered on a 4-point Likert Scale ranging from 1 =
strongly disagree to 4 = strongly agree (sample items included, “Most of the time neither of us
has a condom available”). The subscale was used again at post-test to assess for participants’
condom use barriers in the last month (e.g., “Please answer the following questions based on
your experience over the course of the last month”). Scores were summed and could range from
6 to 24 (pre-test, M = 10.85, SD = 3.73; post-test, M = 11.12, SD = 4.17), with higher scores
indicating greater perception of barriers to condom use. These items demonstrated good
reliability and had a Cronbach alpha of 0.78 at pre-test and 0.82 at post-test.
Condom use self-efficacy. Condom use self-efficacy is defined as an individual’s
confidence in his or her ability to successfully use a condom during sex. To measure it two
subscales (assertiveness and mechanics) from the Condom Use Self-Efficacy Scale (CUSES;
Brafford & Beck, 1991) were used at pre- and post-test (e.g., “I feel confident in my ability to put
a condom on myself or my sexual partner.” and “I feel confident in my ability to suggest using a
condom without my sexual partner feeling diseased”). The seven items were answered on a 5-
point scale ranging from 1 = strongly disagree to 5 = strongly agree. The subscales were used
again at post-test to assess for participants’ condom use self-efficacy since the last survey (e.g.,
“Please answer the following questions based on your experience over the course of the last
month”). Items from both subscales were combined and summed to determine participants’
condom use self-efficacy. Scores could range from 7 to 35 (pre-test, M = 29.85, SD = 4.01;
posttest, M = 30.71, SD = 4.78), with higher scores indicating greater condom use self-efficacy.
In the present sample Cronbach alpha was 0.77 at pre-test and 0.89 at post-test.
Intentions. Participants’ intentions to use condoms in the future were assessed at posttest
using three items developed by Agnew (1998). Responses were on a 7-point Likert scale ranging
from 1 = definitely to 7 = definitely not (e.g., “I intend to use a condom over the next month”).
Scores were summed and could range from 3 to 21(pre-test, M = 8.90, SD = 6.61; post test, M =
9.09, SD = 6.55), with higher scores indicating lower condom use intentions. These items
demonstrated adequate reliability and had a Cronbach alpha of 0.93. Similarly, participants’
intentions to gain knowledge about their PSH were also assessed at post-test using three items on
a 4-point Likert scale ranging from 1 = definitely to 4 = definitely not (e.g., “Within the next
month I intend on asking my partner about their history of being tested for STIs and HIV,”
15

“Within the next month I intend to ask my partner about their history of having concurrent sexual
partners,” “Within the next month I intend to ask my partner about whether or not they have been
diagnosed or treated for a STI”). Scores were summed and could range from 3 to 12 (pre-test, M
= 7.19, SD = 3.26; post test, M = 6.63, SD = 3.01), with higher scores indicating lower intentions
to gain knowledge about a PSH. Cronbach alpha was 0.94 in the present sample.
Partner sexual history. Participants’ knowledge of their PSH was assessed at pre- and
post-test using 12 items on a 5-point Likert scale ranging from 1 = strongly disagree to 5 =
strongly agree (e.g., “My partner has opened up to me about his or her prior sexual
relationships,” and “I know whether or not my current partner has been tested for sexually
transmitted infections since we started dating”). Scores were summed and could range from 12
to 60 (pre-test, M = 51.42, SD = 11.92; post-test, M = 51.68, SD = 12.26), with higher scores
indicating greater knowledge about a PSH. Cronbach alpha was 0.95 at pre- and post-test.
Commitment. Commitment was assessed at pre-test using a short form of the dedication
subscale from Stanley and Markman’s (1992) commitment measure. The scale was comprised of
four items (e.g., “My relationship with my partner is more important to me than almost anything
else in my life,” “I want this relationship to stay strong no matter what rough times we may
encounter”). Questions were answered on a 5-point Likert scale ranging from 1 = strongly
disagree to 5 = strongly agree. Scores were summed and could range from 4 to 20 (M = 15.81,
SD = 2.96) with higher scores indicating greater commitment. Cronbach alpha was 0.69 in the
present sample.
Relationship satisfaction. Following Fincham and Bradbury’s (1987) suggestion
relationship satisfaction was limited to subjective assessments of the relationship at pre-test.
Four items from an Item Response Theory analysis of the Couple Satisfaction Index (Funk &
Rogge, 2007) were adopted to measure relationship satisfaction, including quality (from 1 =
worse than all others/extremely bad to 6 = better than all others/extremely good), reward (from 1
= not at all to 6 = very much or extremely), warmth and comfort (from 1 = strongly disagree to 6
= strongly agree), and happiness (from 1 = extremely unhappy to 7 = perfect). Sample items
included, “I have a warm and comfortable relationship with my partner.” and “How rewarding is
your relationship with your partner?” Scores were summed and could range from 4 to 25 (M =
20.85, SD = 2.75), with higher scores indicating greater satisfaction. Cronbach alpha was 0.81 in
the present sample.
16

Trust. The Dyadic Trust Scale (Larzelere & Huston, 1980) is an 8-item scale measure
that was administered at pre-test to assess participants’ level of trust in their romantic
relationships (e.g., “My partner is truly sincere in his (her) promises”). Answers were given on a
7-point Likert scale ranging from 1= strongly disagree to 7= strongly agree. Scores were
summed and could range from 8 to 56 (M = 48.22, SD = 7.07), with higher scores indicating
greater trust. Cronbach alpha was 0.83 in the present sample.
Sexual communication. The Dyadic Sexual Communication Scale (DSC; Catania, 1986)
has been used in sexual-risk studies to assess individuals’ perceptions of their sexual
communication processes. Several modified versions of the scale have been developed and
administered, including a shortened, four-item version (e.g., Choi et al., 1994) used in this study,
at pre-test. Answers were measured on a 6-point Likert scale (1= disagree strongly, 6 = agree
strongly) to items such as, “Talking about sex is a satisfying experience for both of us,” and “My
partner has no difficulty talking to me about his or her sexual feelings or desires.” Scores were
summed and could range from 6 to 24 (M = 20.54, SD = 3.36), with higher scores indicating
greater communication. Cronbach alpha was 0.81 in the present sample.
Hooking up. Participants provided information about their hooking up experiences using
a single item at pre-test. Before answering the question participants were provided a definition
for hooking up (i.e., “Some people say that a hook up is when two people get together for a
physical encounter and don’t necessarily expect anything further…”). Students where then
asked, “Based on this definition, how many different people did you ‘hookup’ with in the past 12
months?” Responses ranged from 0 (no hook ups) to 9 (8 or more hook ups).
STI testing. Participants’ STI testing history was assessed at pre-test (e.g., “Have you
ever been tested for sexually transmitted diseases?”). Responses were coded 0 = yes and 1 = no.
At pre-test participants also reported when they were last tested (e.g., “When was the last time
you were tested for a sexually transmitted disease?”).
Power
A power analysis was conducted using GPower (Erdfelder, Faul, & Buchner, 2006). It
showed that 51 individuals per treatment condition (using a one-tail test with a p-value of 0.05)
were needed to achieve a power of 0.8, a widely recommended level for research (Cohen, 1988).
Since the smallest group (the treatment group) exceeded this number (n = 89), there was
sufficient power to detect treatment effects. With regards to the last model, power analysis
showed that 101 participants in exclusive relationships were needed accept the outcomes of the
17

statistical test with confidence (using a one-tail test with a p-value of 0.05 and power of 0.8). The
sample included 108 participants, which suggests it was adequately powered.
Analytic Approach
Data from individuals who reported as single or in exclusive dating relationships was
used to test Hypotheses 1-2, but only data from those individuals in exclusive relationships (n =
108) was used to test Hypotheses 3-5. The data were assessed for inconsistent or abnormal
values by looking for skewness and kurtosis (values greater than +3 or less than -3).
Mahalanobis distance was used to check for multivariate normality for each variable (the
maximum Mahalanobis distance should not be greater than the chi-square critical value, with
degrees of freedom equal to the number of predictors and p = 0.001). Using p = 0.001 as the
criterion for Mahalanobis distance, no outliers among the cases were detected. Qualitative data
from the writing activity assigned to students in the treatment condition was used to provide
supplementary information about the treatment outcomes. Furthermore, despite evidence that
links condom use to birth control use (e.g., Leigh et al., 2008) preliminary findings from this
study showed that birth control was not a good predictor of condom use, p = 0.88. Thus, we
refrained from controlling for birth control use in the present study.
To examine the first hypothesis, a repeated measures ANOVA was used to evaluate safe
sex outcomes among participants in the treatment and comparison group. Participants from both
conditions were tested at two points, at baseline and then again 4 weeks after the intervention.
Safe sex practice items (i.e., condom use, condom use self-efficacy, and knowledge of PHS) were
the primary outcome variables. Treatment condition was the independent variable.
Several factors determined the design of this study. A repeated measure design is often
employed by researchers to assess treatment effects (Keselman, 1998) and, more specifically is
used to test sexual health education interventions (e.g., Garofalo et al., 2012; LaBrie, Pedersen,
Thompson, & Earleywine, 2008). Further, repeated measures designs are considered powerful
because they yield a smaller error term, and allow for smaller sample sizes. Since all individual
difference sources of variability are eliminated from the experiment they provide better precision
for comparing condition effects. A repeated measures ANOVA, which is one of the most
frequently used approaches to repeated measures designs, compares the equality of two or more
groups. It is also widely used to analyze two-group randomized experimental studies (e.g., Kirk,
2009). The research design is generally considered more powerful than an independent ANOVA
18

and appropriate for longitudinal designs that have relatively few time points for each subject
(Locascio & Atri, 2011).
Despite having several dependent variables in this study a multivariate analysis of
variance (MANOVA) test was not used due to its limitations. Findings from MANOVA tests are
more ambiguous about the effects of independent variables on any single dependent variable. It
is difficult to identify whether or not the affect of an independent variable on a dependent
variable actually exists or if the affect is a result of multiple dependent variables having an affect
on each other (Salkind, 2010). Consequently, this may lead to subjective assumptions being
drawn (French, Macedo, Poulsen, Waterson, & Yu, 2008). Further, for each dependent variable
that is added one degree of freedom is lost. The added power received from decreasing SS error
may be counteracted by the loss in degrees of freedom. Finally, the dependent variables should
to a large extent be uncorrelated. If they are not, there is little benefit in including more than one
in the test given the consequential loss in degrees of freedom. In regards to the present study,
previous research suggests that there is a strong, significant link between two of the dependent
variables, condom use and condom use self-efficacy (e.g., Crosby et al., 2011). Accordingly,
findings from this study show there was a positive correlation between condom use and condom
use self-efficacy, r = 0.17, p = < 0.05 and a positive correlation between knowledge about a PSH
and condom use self-efficacy, r = 0.19, p = < 0.01 (see Table 1). Given these several limitations
a repeated measure ANOVA test was preferable.
Mediation is commonly tested using the Sobel (1982) method, which assumes that the
product of coefficients constituting the indirect effect is normally distributed. However, since the
distribution tends to be skewed and leptokurtic (Preacher & Hayes, 2008) resampling or
bootstrapping methods are replacing the Sobel method (Shrout & Bolger, 2002). Estimation of
the mediation effect (condition → condom use intentions → post-test condom use and condition
→ intentions to gain knowledge about a PSH → post-test knowledge about a PSH) was
calculated with 2,000 bootstrap samples using the Model Indirect option in Mplus 6.0 to test the
statistical significance of the indirect effects (Muthén & Muthén, 1998-2010).
Finally, using SPSS software, a linear regression analysis was used to identify the extent
to which relationship dimensions (i.e., relationship satisfaction, trust, commitment, and
communication) were associated with sexual risk outcomes among individuals in exclusive
relationships (Hypotheses 3-5). To test these hypotheses, participants in both conditions
completed a series of questionnaires (at pre-test) about their relationship with their current
19

romantic partner. Predictors were identified as factors theoretically or empirically assumed to be
significantly linked to the treatment conditions. Separate multiple regression analyses were run
for each criterion variable (condom use, knowledge about a PSH, and condom use self-efficacy
at post-test). Within each analysis, relationship factors (i.e., relationship satisfaction, trust,
commitment, and communication), condition, and sexual outcomes at pre-test (i.e., condom use,
knowledge about a PSH, and condom use self-efficacy at pre-test) were simultaneously entered
as predictor variables.
CHAPTER THREE
RESULTS
Descriptive Statistics
Information about participants’ sexual health risk was collected (see Table 3). One-third
of participants in the general sample reported never being tested for a STI (37%). When
participants in exclusive relationship were asked when they were last tested for a STI, 32% said
they had never been tested, 13% stated while in their current romantic relationship, but before
they had penetrative sex. Almost three times as many (35%) reported that they had been tested,
but only after having penetrative sex with their partner. Seven percent reported getting tested
after their relationship ended, and 13% percent stated they did not remember when they were last
tested. Of those who were not in exclusive relationships 92% reported engaging in a hookup at
least once in the last 12 months, while 70% reported engaging at least two or more hookup
encounters.
Treatment Effects on Sexual Risk Outcomes
A repeated measure 2 (group: sexual negotiation education vs. traditional sexual health
education) x 2 (time: pre vs. post) split plot ANOVA was used. Statistical Package for Social
Sciences (SPSS) software was used to conduct this analysis. Main effects and interactions were
examined in each analysis. When a significant interaction was found, simple effects tests were
conducted for both the treatment and comparison group using repeated measure ANOVA, but
without the inclusion of grouping variables. Hypothesis 1a, predicted that students in the
treatment condition would engage in greater condom use than those in the comparison condition.
20

The means and standard deviations for the sample are shown in Table 4. Results from the
repeated measure ANOVA revealed an interaction effect between condition and time on condom
use, F(1, 168) = 5.61, p = 0.02, η2p = 0.03 (see Table 5). Follow up simple main effects tests
supported the first hypothesis, showing that participants in the treatment condition were
significantly more likely to report greater condom use at post-test, F(1, 85) = 11.49, p = 0.001,
η2p = 0.12 than at pre-test. Participants in the comparison condition however, were not
significantly more likely to report greater condom use at post-test, F(1, 83) = 0.06, p = 0.81, η2p =
0.01 than at pre-test.
Hypothesis 1b, predicted that that students in the treatment condition would be more
likely to report greater knowledge about their PSH than those in the comparison condition at
post-test than at pre-test. Despite finding a marginally significant interaction effect between the
condition and time on gaining knowledge about PSH, F(1, 161) = 3.91, p = 0.05, η2p = 0.02 (see
Table 6), follow up simple main effects tests showed participants in the treatment, F(1, 83) =
1.93, p = 0.17, η2p = 0.02 and comparison condition F(1, 78) = 1.97, p = 0.16, η2p = 0.03, were not
significantly more likely to report having greater knowledge about their PSH at post-test than at
pre-test. Thus, findings showed no support for Hypothesis 1b. Also, no significant interaction
effect between condition and time on condom use self-efficacy was found, F(1, 166) = 1.46, p =
0.23 η2p = 0.01 (see Table 7). Therefore, there was no support for Hypothesis 1c, which predicted
that students in the treatment condition would be more likely to report greater condom use self-
efficacy than those in the comparison condition at post-test than at pre-test.
To examine possible gender differences a 2 (group: sexual negotiation education vs.
traditional sexual health education) x 2 (time: pre vs. post) x 2 (gender: men vs. women) factorial
ANOVA was conducted with time as a repeated measure. Results from the post-hoc analysis
showed that there was not a significant 3-way interaction between gender, condition, and time on
condom use, F(1, 164) = 0.06, p = 0.81, η2p = 0.00. However, there was a significant 2-way
interaction between gender and time on condom use, F(1, 164) = 5.43, p = 0.02, η2p = 0.03.
Follow up simple effects tests showed that women were significantly more likely to report
greater condom use at post-test than at pre-test, F(1, 140) = 11.26, p < 0.001, η2p = 0.07 in
comparison to men, F(1, 26) = 1.55, p = 0.22, η2p = 0.06. The means and standard deviations for
the sample are shown in Table 8.
Results from a similar ANOVA also showed that there was not a significant 3-way
interaction between gender, condition, and time on knowledge about a PSH, F(1, 157) = 0.45, p
21

= 0.50, η2p = 0.00. There was also not a significant 2-way interaction effect between gender and
time on knowledge about a PSH, F(1, 157) = 0.01, p = 0.93, η2p = 0.00. Additionally, there was
not a significant 3-way interaction between gender, condition, and time on condom use
selfefficacy, F(1, 163) = 0.70, p = 0.40, η2p = 0.00. There was also not a significant 2-way
interaction between gender and time on condom use self-efficacy, F(1, 163) = 0.78, p = 0.77, η2p
= 0.00.
Intention Mediation
A mediation path analysis with a bootstrapped indirect effect estimation method was used
to test whether condom use intentions and intentions to gain knowledge about a PSH mediated
the relationship between the treatment and criterion variables (i.e., condom use and knowledge
about a PSH; Hypothesis 2). Findings from the analysis did not show support for Hypothesis 2a
(see Figure 3). The effect of condition on condom use intentions was not statistically significant,
β = 0.04, p = 0.38. However, the effect of condom use intentions on post-test condom use was
statistically significant, β = -0.72, p > 0.001. The indirect path through intentions to use
condoms showed no mediation effect and was not statistically significant, as indicated by
findings that the 95% Confidence Interval (bias corrected) for the indirect path captured zero,
95% CI [-0.10, 0.04]. Additionally, the direct effect between the predictor and criterion variable
remained significant (p > 0.001) when the mediator was introduced. Altogether this
demonstrates that condom use intentions did not explain the relationship between the condition
and post-test condom use.
As regards to Hypothesis 2b, the effect of condition on intentions to gain knowledge
about a PSH and the effect of intentions to gain knowledge about a PSH on post-test knowledge
about a PSH were not significant (β = 0.06, p = 0.58 and β = -0.06, p = 0.56, respectively, see
Figure 4). The indirect path through intentions to gain knowledge about a PSH showed no
mediation effect and was not statistically significant as indicated by findings that showed the
95% Confidence Interval (bias corrected) for the indirect path included zero, 95% CI [-0.02,
0.01].
Association of Relationship Factors with Sexual Risk Outcomes
In testing to see whether or not relationship factors were linked to sexual risk outcomes at
post-test a linear regression analysis was used. Hypothesis 3a, examined whether or not
relationship factors (i.e., relationship satisfaction, trust, commitment, and communication) were
associated with condom use at post-test (see Table 9). Relationship satisfaction was significantly
22

associated with condom use at post-test, β = -0.34, t(103) = -2.34 p = 0.02, and remained so even
when controlling for condition, and condom use at pre-test, β = -0.28, t(101) = -2.63, p = 0.01.
More specifically, participants who reported greater levels of relationship satisfaction were less
likely to report using condoms with their exclusive partner at post-test. Conversely, support for
Hypotheses 3b-3d was not found. The trust (p = 0.75), commitment (p = 0.17), and
communication (p = 0.51) variables were not significantly associated with condom use at
posttest.
To test Hypotheses 4a-4d, I examined whether or not relationship factors were associated
with individuals’ knowledge about PSH at post-test. Findings indicated no support for the
Hypotheses. The relationship satisfaction (p = 0.66), trust (p = 0.55), commitment (p = 0.14),
and communication (p = 0.71) variables were not significantly associated with individuals’
knowledge about their PSH at post-test. Further, no support was found for Hypotheses 5a-5d.
Relationship satisfaction (p = 0.57), trust (p = 0.23), commitment (p = 0.47), and communication
(p = 0.97) were not significantly associated condom use self-efficacy at post-test.
Possible gender differences were examined through interactions with the predictor
variables (i.e., relationship factors) using hierarchical linear regression in SPSS. No significant
interactions between gender and each of the relationship factors emerged. More specifically,
there was not a difference between men and women on the association between condom use at
post-test and relationship satisfaction, β = -0.01, t(91) = -0.06, p = 0.95, ∆R2= 0.00; trust, β =
0.01, t(91) = -0.07, p = 0.95, ∆R2 = 0.00; β = -0.02, commitment, t(91)= -0.24, p = 0.81, ∆R2 =
0.00; and communication, β = -0.03, t(91)= -0.47, p = 0.64, ∆R2 = 0.00 when controlling for
condition and condom use at pre-test.
Similarly, there were no interactions between gender and each relationship factor on
knowledge about a PSH. Findings showed that the association between knowledge about a PSH
at post-test and relationship satisfaction, β = -0.02, t(89)= -0.22, p = 0.83, ∆R2 = 0.00; trust, β =
0.02, t(89) = -0.23, p = 0.82, ∆R2 = 0.00; commitment β = -0.02, t(89)= -0.29, p = 0.78, ∆R2 =
0.00; and communication, β = -0.02, t(89) = -0.32, p = 0.75, ∆R2 = 0.00 did not differ by gender,
when controlling for condition and knowledge about a PSH at pre-test. There were also no
interactions between gender and each relationship factor on condom use self-efficacy. Results
showed that the association between condom use self-efficacy at post-test and relationship
satisfaction, β = 0.05, t(91) = 0.59, p = 0.56, ∆R2 = 0.00; trust, β = 0.05, t(91) = -0.23, p = 0.82,
∆R2 = 0.00; commitment, β = 0.05, t(91) = 0.60, p = 0.55, ∆R2 = 0.00; and communication, β =
23

0.05, t(91) = 0.62, p = 0.53, ∆R2 = 0.00 did not differ by gender, when controlling for condition
and condom use self-efficacy at pre-test. Thus, again, results did not vary by gender.
CHAPTER FOUR
DISCUSSSION AND IMPLICATIONS
Using a randomized sample, I examined (a) the impact of sexual negotiation training as
compared to standard sexual health education on reducing sexual risk-taking among college
students, (b) how intentions mediated the relationship between the condition and post-test sexual
risk outcomes, among students who received sexual negotiation training, and (c) how various
relationship factors were linked to sexual risk outcomes at post-test, among college students in
exclusive dating relationships. Overall, there was some evidence to suggest that sexual
negotiation training can be effective at reducing college students’ sexual risk.
Although the use of condoms is critical in the prevention of STIs and HIV condom use
among college students is inconsistent (e.g., Lewis et al., 2009). This highlights the importance
of the first analysis, which showed that condom use significantly increased among those who
received sexual negotiation training (Hypothesis 1a). The finding is also promising given the
brief nature of the intervention and considering how difficult it can be to change condom use
behaviors (Albarracin et al., 2001).
The finding also speaks to the criticism that education programs promote changes in
knowledge, but not in behavior (Ku, Sonenstein, & Pleck, 1992) and to previous research that
shows that gaining knowledge about STI and HIV/AIDS does not improve condom use among
college students (Williams, Norris, & Bedor, 2003). Specifically, the present finding suggests
that changes in condom use behavior can occur through the application of skills based education
(i.e., sexual negotiation training). Reports from those who received the sexual negotiation
training (gathered from the writing activity) illustrates how the training provided a benefit that
went beyond providing participants with statistics and general information about condom use.
For example, when asked to explain what they had learned from the sexual negotiation training
session one participant answered, “No matter what you should be comfortable with yourself to
speak up and use a condom…to avoid the consequences afterwards. Just because you may know
24

the person you are with doesn't mean you know what they may have.” Similarly, another
participant stated:
Clearly, it is NOT worth it not to use one. You can never fully trust someone to be honest
with you—you don't know if they have been tested recently or may be with multiple
partners. Having to go to the clinic is more embarrassing than suggesting the use of a
condom.
Sexual negotiation training also appears to help students overcome the barriers they face
when trying to use condoms. Specifically the training does this by providing student sensitive
and safe ways to negotiate condom use. For instance, when asked about what they learned from
the sexual negotiation video to help them address barriers to condom use one participant in the
sexual negotiation group responded, “It helps with trying to face your partner when the time
comes. Sometimes you don’t know how to bring up something like that, but the video helps you
with what to do in those scenarios.” Another person stated, “Always remind yourself that if you
do not know your partner's sexual history, the safest way to protect yourself is through using
protection, like a condom.”
Given the increased use of condoms among those who received sexual negotiation
training in this study and past research findings that positively link condom use and sexual risk
perception (Civic, 1999) sexual negotiation training may help students move beyond their
perception of risk and toward the reality of their actual risk. This is important, because despite
the barriers to condom use (Corbett et al., 2009) and the prevalence of sexual risk taking among
college students (Owen et al., 2010), the vast majority of students do not perceive themselves as
being at risk for sexually related infections (Inungu, Mumford, Younis, & Langford, 2009). That
being said, this interpretation of the data (i.e., positively linking condom use and improved risk
perception) is speculative rather than empirically grounded. Overall, the finding calls for
educators to consider conducting sexual negotiation training, as opposed to standard sexual
education, to improve condom use among college students.
Post-hoc analyses revealed a gender difference on condom use at post-test. More
specifically, independent of condition, women in the present study were more likely to report
greater condom use at post-test as compared to men. This finding is important given that
previous research suggests that women are less likely to use condoms as compared to men (e.g.,
Robertson, Stein, and Baird-Thomas, 2006). Moreover, not only is the rate of transmission for
STI and HIV growing more rapidly for heterosexual women than for heterosexual men (CDC,
25

2011b), but as compared to men, women experience more long-term consequences of STIs
(CDC, 2010). Despite being at sexual risk, women tend have a reduced sense of sexual risk and
are less comfortable negotiating condom use with partners (Williams & Semanchuk, 2000).
One study suggests that while heterosexual women have more favorable attitudes about
condom use, they are more likely to have unprotected sex as compared to heterosexual men
(Martínez-Donate et al., 2004). A similar study found that as compared to men, women reported
having greater condom use self-efficacy, a greater perceived sense of sexual risk, and better
attitudes about condom use, but were less likely to report actual condom use (Robertson et al.,
2006). Women are also more likely to be in the vulnerable position of having to negotiate
condom use, while men have been found to be more reactive in the negotiation process (Carter,
McNair, Corbin, & Williams, 1999).
Additionally, despite the opportunity for women to wear female condoms, most women
expect men to wear condoms (Gollub, 2000). Some women complain that the female condom is
unattractive, too large, makes too much noise during coitus, is uncomfortable, and is difficult to
maintain in place (Buck et al., 2005). Female condoms are also more expensive then male
condoms. Consequently, by not wearing condoms many women become dependent on men for
protection and more susceptible to sexual risks. Conversely, given that men are typically the ones
that wear condoms, men may have a greater perceived sense of control over their condom use
(Beadnell, Baker, Morrison, & Knox, 2000).
A considerable body of literature also suggests that gender related power imbalances puts
women at greater sexual risk as compared to men (e.g., Pulerwitz et al., 2002). For example,
gender scripts and roles have historically discouraged women from initiating discussions about
sex. Consistent with this, some studies suggest that complying with more conventional sex roles
has created barriers for women that have kept them from successfully negotiating condom use
with their partners (e.g., Beadnell et al., 2000). Women who provide their own condoms are also
viewed less favorably and as more promiscuous compared to men. Overall, previous findings
show that women engage in less condom use and are disproportionately at greater risk of
contracting a STI and HIV as compared to heterosexual men. This may explain, in part, why
sexual education programs have primarily targeted women in the United States (Seal & Ehrhardt,
2004). Additionally, previous findings provide evidence for why sexual negotiation training may
be particularly important for women attending college.
26

Conversely, the role men play in the use of condoms should not be underestimated.
Condoms are still mainly managed and purchased by men. Despite this sexual education
programs typically assume that women and not men should be the primary recipients of
negotiation training (Otto-Salaj et al., 2008). Tentative findings from the male sample in the
present study, in accordance with recommendations made by Seal and Ehrhardt (2004), suggest
the need for training programs that are more effective at improving condom use among men.
Findings from a more recent study by Labrie et al. (2008) show that motivational interviewing
may be one way to help improve male college students’ condom use. The tentative gender
difference found in this study also supports previous research suggesting the need for sexual
education research that adequately examines the effects of gender related factors (i.e., gender
roles and relationship power), on both men and women’s willingness and ability to engage in
greater condom use (e.g., Amaro, 2000; Pulerwitz, Amaro, De Jong, Gortmaker, & Rudd, 2002).
This was also the first study to examine how sexual health education training impacted
individuals’ knowledge about their PSH. In contrast to Hypothesis 1b, knowledge about PSH did
not significantly increase among those who received sexual negotiation training, as compared to
those in the comparison group. Thus, it appears that receiving sexual negotiation training may
improve condom use, but it does not effect whether or not individuals communicate with their
partner about their PSH. Gaining knowledge about a PSH can improve condom use (Crosby,
Yarber, Diclemente, Wingood, & Meyerson, 2002), decrease one’s number of sexual partners
(Catania, 1989) and is key to reducing the transmission of STIs and HIV. However, despite the
importance of talking about past sexual histories, the conversation is a difficult one to have with
partners. That is why sexual negotiation training programs should expand their curricula to
include implicit and explicit messages that address the importance of talking with partners about
past sexual histories.
Perhaps another reason why participants who received sexual negotiation training did not
improve their knowledge about their PSH was not due to a lack of effort, but a lack of success
(e.g., partners refusing to share information). Congruent and honest communication requires at
least two people and is a reciprocal process (Satir, 1983; Satir & Baldwin 1983). Moreover,
according to family systems theory, systemic based interventions are the best mechanism through
which problems are resolved and meaningful changes in interaction occur (e.g., Gale &
27

Long, 1996). Thus, findings from literature that supports the use of systemic based interventions
to improve interaction processes may explain why no significant improvements in knowledge
about a PSH were found among those who received sexual negotiation training.
Also, despite previous research that suggests 20-25% of individuals in close relationships
are unaware of their PSH (EDK, 1995) many participants in the present study had considerably
high scores on measures that assessed their knowledge of their PSH. Otherwise stated, findings
from this study show a ceiling effect (scores were concentrated toward the higher end of the
5point Likert scale used to measure knowledge about a PSH). This may also explain why no
significant differences were found between those in the treatment and comparison group on
knowledge about a PSH. Additionally, higher responses may reflect the belief that one can know
whether or not their partner has a STI just by looking at them. This idea is consistent with
findings from other studies that suggest that college students base their perceived knowledge of
their partner’s sexual health on intuition and superficial qualities (i.e., attractiveness and whether
they look clean and healthy; Noar, Zimmerman, Atwood, & 2004).
Furthermore, findings comparing condom use self-efficacy between those in the treatment
and comparison conditions (Hypothesis 1c) showed that condom use self-efficacy did not
significantly increase among those in the treatment or comparison group. These findings are in
contrast to similar findings that show a link between receiving sexual negotiation training and
improved condom use self-efficacy (Sanderson & Yopyk, 2007). Given that condom use
selfefficacy is an important predictor of condom use (e.g., Crosby et al., 2011) it is surprising that
unlike actual condom use, condom use self-efficacy did not significantly improve among those
who received sexual negotiation training. That said, a ceiling effect might also explain why no
difference was found in condom use self-efficacy between those in the treatment and comparison
group. Results from the data showed that scores were concentrated toward the higher end of the
5-point Likert scale used to measure condom use self-efficacy. Altogether, the finding
demonstrates the multidimensionality of condom use self-efficacy (Baele, Dusseldorp, & Maes,
2001) and suggests the need for research that tests for psychosocial factors that moderate the
relationship between condom use self-efficacy and actual condom use among college students.
Findings for Hypothesis 2a showed that condom use intentions did not mediate the
relationship between condition and condom use at post-test. More specifically, differences in
condom use at post-test between those who received sexual negotiation training and those who
received standard sexual health education were not associated with condom use intentions. Also,
28

there appeared to be no relationship between condition and condom use intentions at post-test.
Despite participants in the treatment group reporting greater condom use, they are no more likely
to have greater intentions to use condoms than those in the comparison group. This finding is
somewhat surprising given previous research that links condom use intentions and actual condom
use (Albarracin et al., 2001) and also given that sexual education has been found to improve
condom use intentions (Bryan et al., 2006). Additionally, since past findings show that intentions
are a proximal determinant of behavior (Ajzen, 1991) this finding begs the question, if not a
change in intentions to use condoms, what is it about receiving the treatment that accounted for
improved condom use among those in the treatment group? Additionally, no support was found
for Hypothesis 2b, which suggests that intentions to gain knowledge about PSH do not mediate
the link between condition and knowledge about PSH at post-test. Thus, differences in
knowledge about PSH at post-test between those who received sexual negotiation training and
those who received standard sexual health education were not associated with intentions to gain
knowledge about a PSH.
Findings from the mediation analyses in this study suggest that the link between
intentions and changes in behavior is multidimensional, and that intentions may not always be
proximally linked to behaviors. For instance, college students may have every intention to
engage in safe sex practices. However, certain behaviors that reduce safe sex practices are
common among college students, including unplanned hookups and frequent binge drinking (e.g.
Parks et al., 2009), and may stand in the way of them executing those intentions. Also, group
conformity and approval is important for many college students and may explain why some
engage in risky sexual behavior (Paul & Hayes, 2002). Thus, despite all their good intentions, the
aforementioned barriers may be what explain college students’ safe sex practices, not intentions.
Perhaps this may also explain why intentions did not mediate the relationship between the
treatment and sexual risk reduction outcomes in the present study.
In spite of research that shows a link between sexual risk behaviors and relationship
factors, this was also the first study to examine how relationship factors were linked to sexual
risk outcomes among college students who received sexual health education. Past research
suggests that trust, commitment, and communication are good indicators of condom use (Brady
et al., 2009; Harvey et al., 2006; Otto-Salaj et al., 2008); however, the findings in this study
showed that they were not good indicators of condom use among individuals who received any
form of sexual health education. This suggests that sexual health education may be effective at
29

addressing these relationship factors in a way that eliminates them as barriers to condom use.
This makes sense, given that scenes from the video and information in the essays were based on
individuals in exclusive relationships. Information from the PowerPoint and video also
illustrated the risks associated with having multiple partners. Additionally, the dialogue used in
the training highlighted the importance of sexual communication and trust within dyadic
relationships.
In contrast, the link between relationship satisfaction and condom use appears to be
important among those in exclusive dating relationships. This is consistent with past research
that shows those in more satisfying relationships are less likely to use condoms with their
primary partner, as compared to those who are less satisfied in their relationship (e.g., Manning
et al., 2009). Again, this pattern held true even when individuals received sexual health
education. Thus, despite receiving information about the importance of safe sex practices and
skills based training on condom use negotiation within exclusive relationships, it appears that
individuals in more satisfying relationships perceive themselves to be at reduced risk or find
condom use to be a threat to the status quo of their relationship.
This finding provides support for existing research that suggests that individuals in
exclusive relationships exercise safe sex practices based on the potential consequences it may
have on their primary relationship (e.g., Umphrey & Sherblom, 2007). Knowledge and skill
based sexual health education programs may benefit from curricula that make a distinction
between being happy in a relationship versus being at sexual-risk in a relationship, so that
students have a clear sense of how to assess their risk. Providing additional information about
how common it is for many STIs to go undiagnosed (even among people who appear to be in
highly satisfying relationships), may be one way to increase risk perception and condom use.
Additionally, helping individuals identify and adopt solutions to the challenges associated with
negotiating condom use in a highly satisfying relationship may help improve condom use among
this subgroup.
Past research also suggests a link between relationship factors and gaining information
about PSH (e.g., Bolton, 2009). However, findings from the present study showed that
relationship factors (i.e., relationship satisfaction, trust, commitment, and communication) were
not significant indicators of gaining information about PSH among individuals who received
sexual health education. Perhaps receiving sexual health education helps individuals in exclusive
dating relationships communicate in more detail about safe sex practices, which may in turn be
30

effective at addressing relationship factors in a way that eliminates them as barriers to gaining
knowledge about PSH. Additionally, a link between relationship factors and condom use self-
efficacy has also been found in the literature (e.g., Das & Teng, 1998; Farmer & Meston, 2006).
However, in this study relationship factors did not appear to be linked to condom use self-
efficacy among individuals in exclusive relationships who received sexual health education. Said
differently, relationship factors may not act as barriers to improving condom use selfefficacy
among students who receive sexual health education. Additionally, post-hoc analyses showed
that gender did not account for any more of the variance in the criterion variables (condom use,
knowledge about a PSH, and condom use self-efficacy) when controlling for all other factors.
Otherwise stated, the strength of the relationship between relationship factors and sexual
outcomes does not appear to be associated with gender.
Limitations and Future Research
This study is not without its limitations. Some major disadvantages of surveys are that
responses tend to be influenced by how instruments are organized and by the way in which items
are worded (Prus & Johnson, 1994). Additionally, forced choice responses may have inhibited
more honest responses. In an effort to reduce these disadvantages standardized instruments used
to assess similar students populations, were employed in this study. Despite these limitations,
some of the disadvantages of self-report data are difficult to resolve and may have reduced the
validity and reliability of the responses in this study. Also, traditional problems with social
desirability response bias may limit the generalizability of these findings. Descriptive analyses
from this study suggest that many participants had high scores on some of the observed variables.
As a consequence, some of the measures may have failed to accurately show the true variability
in scores and the true impact of the intervention on participants’ knowledge about their PSH and
condom use self-efficacy at post-test.
Given the small male sample size findings for males may be statistically underpowered.
Therefore, caution is warranted when drawing conclusions about gender differences in this study.
For instance, despite findings being statistically significant, the virtually equal effect sizes
indicate that the treatment is equally effective at improving condom use for both men and
women. This conclusion is consistent with previous findings that suggest that sexual education
has the same impact for both men and women (Caron, Godin, Otis, & Lambert, 2004). Future
sexual negotiation training based research would do well to include more male participants so
that more accurate conclusions about the impact of sexual negotiation training on sexual risk
31

reduction among male students can be drawn. Perhaps one way to do this is by recruiting from
departments within universities where men comprise a greater percentage of the student
population.
Despite having the appropriate sample size needed to examine the results in the general
treatment comparison, the small sample size in the secondary analyses, made up of those in
exclusive relationships, may limit the strength and conclusions drawn for that subgroup. Also,
despite its advantages, multiple measures where not used to test any one variable in this study
(Prus & Johnson, 1994). A face-to-face skill building activity and a question and answer session
were not included in the intervention due to time constraints and limited resources. Accordingly,
excluding these activities from the intervention may have limited the findings.
Overall, findings from this study provide important information, but also evoke more
questions than answers. In an attempt to address the growing sexual health disparities that exist
by race/ethnicity and sexual orientation this study should be replicated among other groups (i.e.,
gay men, men sleeping with men, Blacks, and Hispanics). Also, it is worth assessing for possible
differences in treatment outcomes between students in exclusive relationships and those who are
single (many of whom engage in hookup encounters), given the different sexual scripts used by
these two subgroups.
Future studies should also use more rigorous measures of the TPB to test the applicability
of the theory as a framework for the development and implementation of sexual negotiation
training programs. Conclusions from the analyses on condom use self-efficacy in this study
suggest that future studies should carefully examine whether or not condom use-self efficacy is
actually a threat to relationships (gaining the confidence to use condoms efficiently is arguably
not as threatening to the intimacy of one’s relationship as actually pulling out a condom and
putting it on a partner or communicating with a partner about their PSH). Future studies should
also examine what relationship factors are linked to condom use-self efficacy. Given the
challenges that many couples face when talking about sex, individuals may not always be
successful at obtaining certain information from their partner about their sexual history. That
said, the measure used to assess participants’ knowledge about their PSH might not have
captured whether or not the sexual negotiation training improved participants’ actual efforts to
gain knowledge about their PSH. Therefore, future studies should examine whether or not sexual
negotiation improves students’ attempts to gain knowledge about their PSH (sample item may
include “I asked my current partner whether or not he was tested for STIs since we started
32

dating”). Moreover, the collection of longitudinal data allows school programs to demonstrate
the added value of using a particular curriculum with student populations (Olds, 2004).
Therefore, future studies should make considerable effort to evaluate the benefits of sexual
negotiation programs using follow up data collected over an extended time period and multiple
intervals.
Lastly, given the wide-ranging benefits of systemic based interventions (Carr, 2009;
Lebow, Chambers, Christensen, & Johnson, 2012; Klann, Hahlweg, Baucom, & Kroeger, 2009;
Shardish & Baldwin, 2005) researchers would do well to conduct couples-based sexual
negotiation training within college settings. Findings from a meta-analytic review of 20 marriage
and family interventions done by Shadish and Baldwin (2003) showed that individuals who
received couples treatment reported greater improvements in their relationship, as compared to
those in a no-treatment group. Also, findings from a review of the literature by Carr (2009)
indicate the importance of couples-based interventions in the treatment of various mental health
disorders (e.g., anxiety disorders, sexual problems, and chronic physical pain; Carr, 2009).
Finally, a more recent decade review of the literature showed that an estimated 70% of couples
that received treatment together showed positive improvement (Lebow et al., 2012, p. 145).
Sexual behaviors and interactions patterns that occur likely reflect the interaction between
partners (DeLamater & Hyde, 2004). Given that most sexual expression occurs interpersonally,
it is no surprise that for several decades systemic models have been used to examine sexual
attitudes and behaviors (e.g., Fish, Fish, & Sprenkle, 1984). In more recent years countless
studies have shown the benefits of couples-based interventions in the prevention and treatment of
sex related outcomes (e.g., Carr, 2009; Markovic, 2007).
With regards to sexual health education, research also shows that intervening with
couples may be more effective at improving safe sex behaviors (Becker, 1996). For instance,
Remien et al. (2005) examined the effects of HIV programs on medication use among HIV
infected participants and found that compared to those who received individual HIV treatment,
participants who received couples-based treatment had greater medication adherence. More
recently, Burton, Darbes, and Operario (2010) also found that couples-based sexual health
education training increased safe sex practices. Thus, despite the challenge of recruiting couples
(Hendriksen et al., 2007) the proven benefits of couple based sexual health education training,
combined with the fact that an estimated half of college students are in exclusive dating
33

relationships at any given time, suggests the need for couples-based sexual health interventions
for students.
Additionally, researchers and educators should consider implementing more rigorous
procedures when conducting couples-based sexual negotiation trainings within college settings.
For instance, some therapists use enactments to create changes in structure and interactions
between members of a unit. Enactments, which are used by relational-based therapists (Davis &
Butler, 2004), are defined as behaviors (i.e., dysfunctional or positive transactional patterns acted
out within treatment) that “stimulate and guide couples interactions as opposed to channeling
interaction through the therapist” (Butler, 1996, p. 27). Enactments are mainly used as a
“medium for mediating relationships through simultaneous experiential intervention and change
at multiple levels of relationships—including specific relationship disagreements and problems”
(Davis & Butler, 2004, p. 319).
Given that enactments have been extensively used in systemic based interventions (i.e.,
marital enrichment programs, emotional focused therapy, structural family therapy, and
behavioral marital therapy) and proven to help couples build new skills in communication, it is
recommended that they be used in future sexual negotiation training interventions. More
specifically, future studies should consider incorporating enactments in couples-based sexual
negotiation training to help facilitate changes in safe sex practices by coaching college couples to
interact more openly about their condom use and past sexual history. Consistent with some of
the procedures implemented by therapists, sexual negotiation training programs should also
incorporate goal setting, behavioral rehearsal (role playing), and affective and cognitive coping
response exercises to assist students who face relational barriers.
Implications
From a public health perspective, implementing useful prevention programs that reduce
risky sexual behaviors is a critical public health issue (CDC, 2009). Though there is
considerable discussion and disagreement among politicians, educators, and the general public as
to how to implement these programs among teenagers (Walcott, Chenneville, & Tarquini, 2011),
there is little discussion about the use of sexual health education programs among young adults
in college (for an exception see Lewis et al., 2009). Given evidence to suggest that a large
number of young adults in college settings engage in at-risk sexual behavior (e.g., Hightow et al.,
2005; Lewis et al., 2009; Owen et al., 2010), it is time to expand sexual negotiation education to
college classrooms. In particular, I propose that sexual negotiation training be employed
34

alongside relationship education, so that college students are provided skills based training that
incorporates a holistic approach to understanding of how relationship factors (i.e., relationship
satisfaction) are linked to sex related attitudes and behaviors (i.e., condom use).
Conclusion
This study carries practical value and to my knowledge is the first study to examine
sexual negotiation training among young adults in a college setting. It is also the first to examine
how relationship factors are linked to sexual risk reduction among college students in exclusive
dating relationships who receive either traditional sexual education or sexual negotiation training.
Overall, findings from this study illustrate the benefits of sexual negotiation training at
improving condom use on college campuses, where nearly 20 million students are enrolled in
any given year (U.S. Census, 2011). Findings from this study also underscore the need to design
sexual health education programs that address relationship characteristics and dynamics on
college campuses.
35
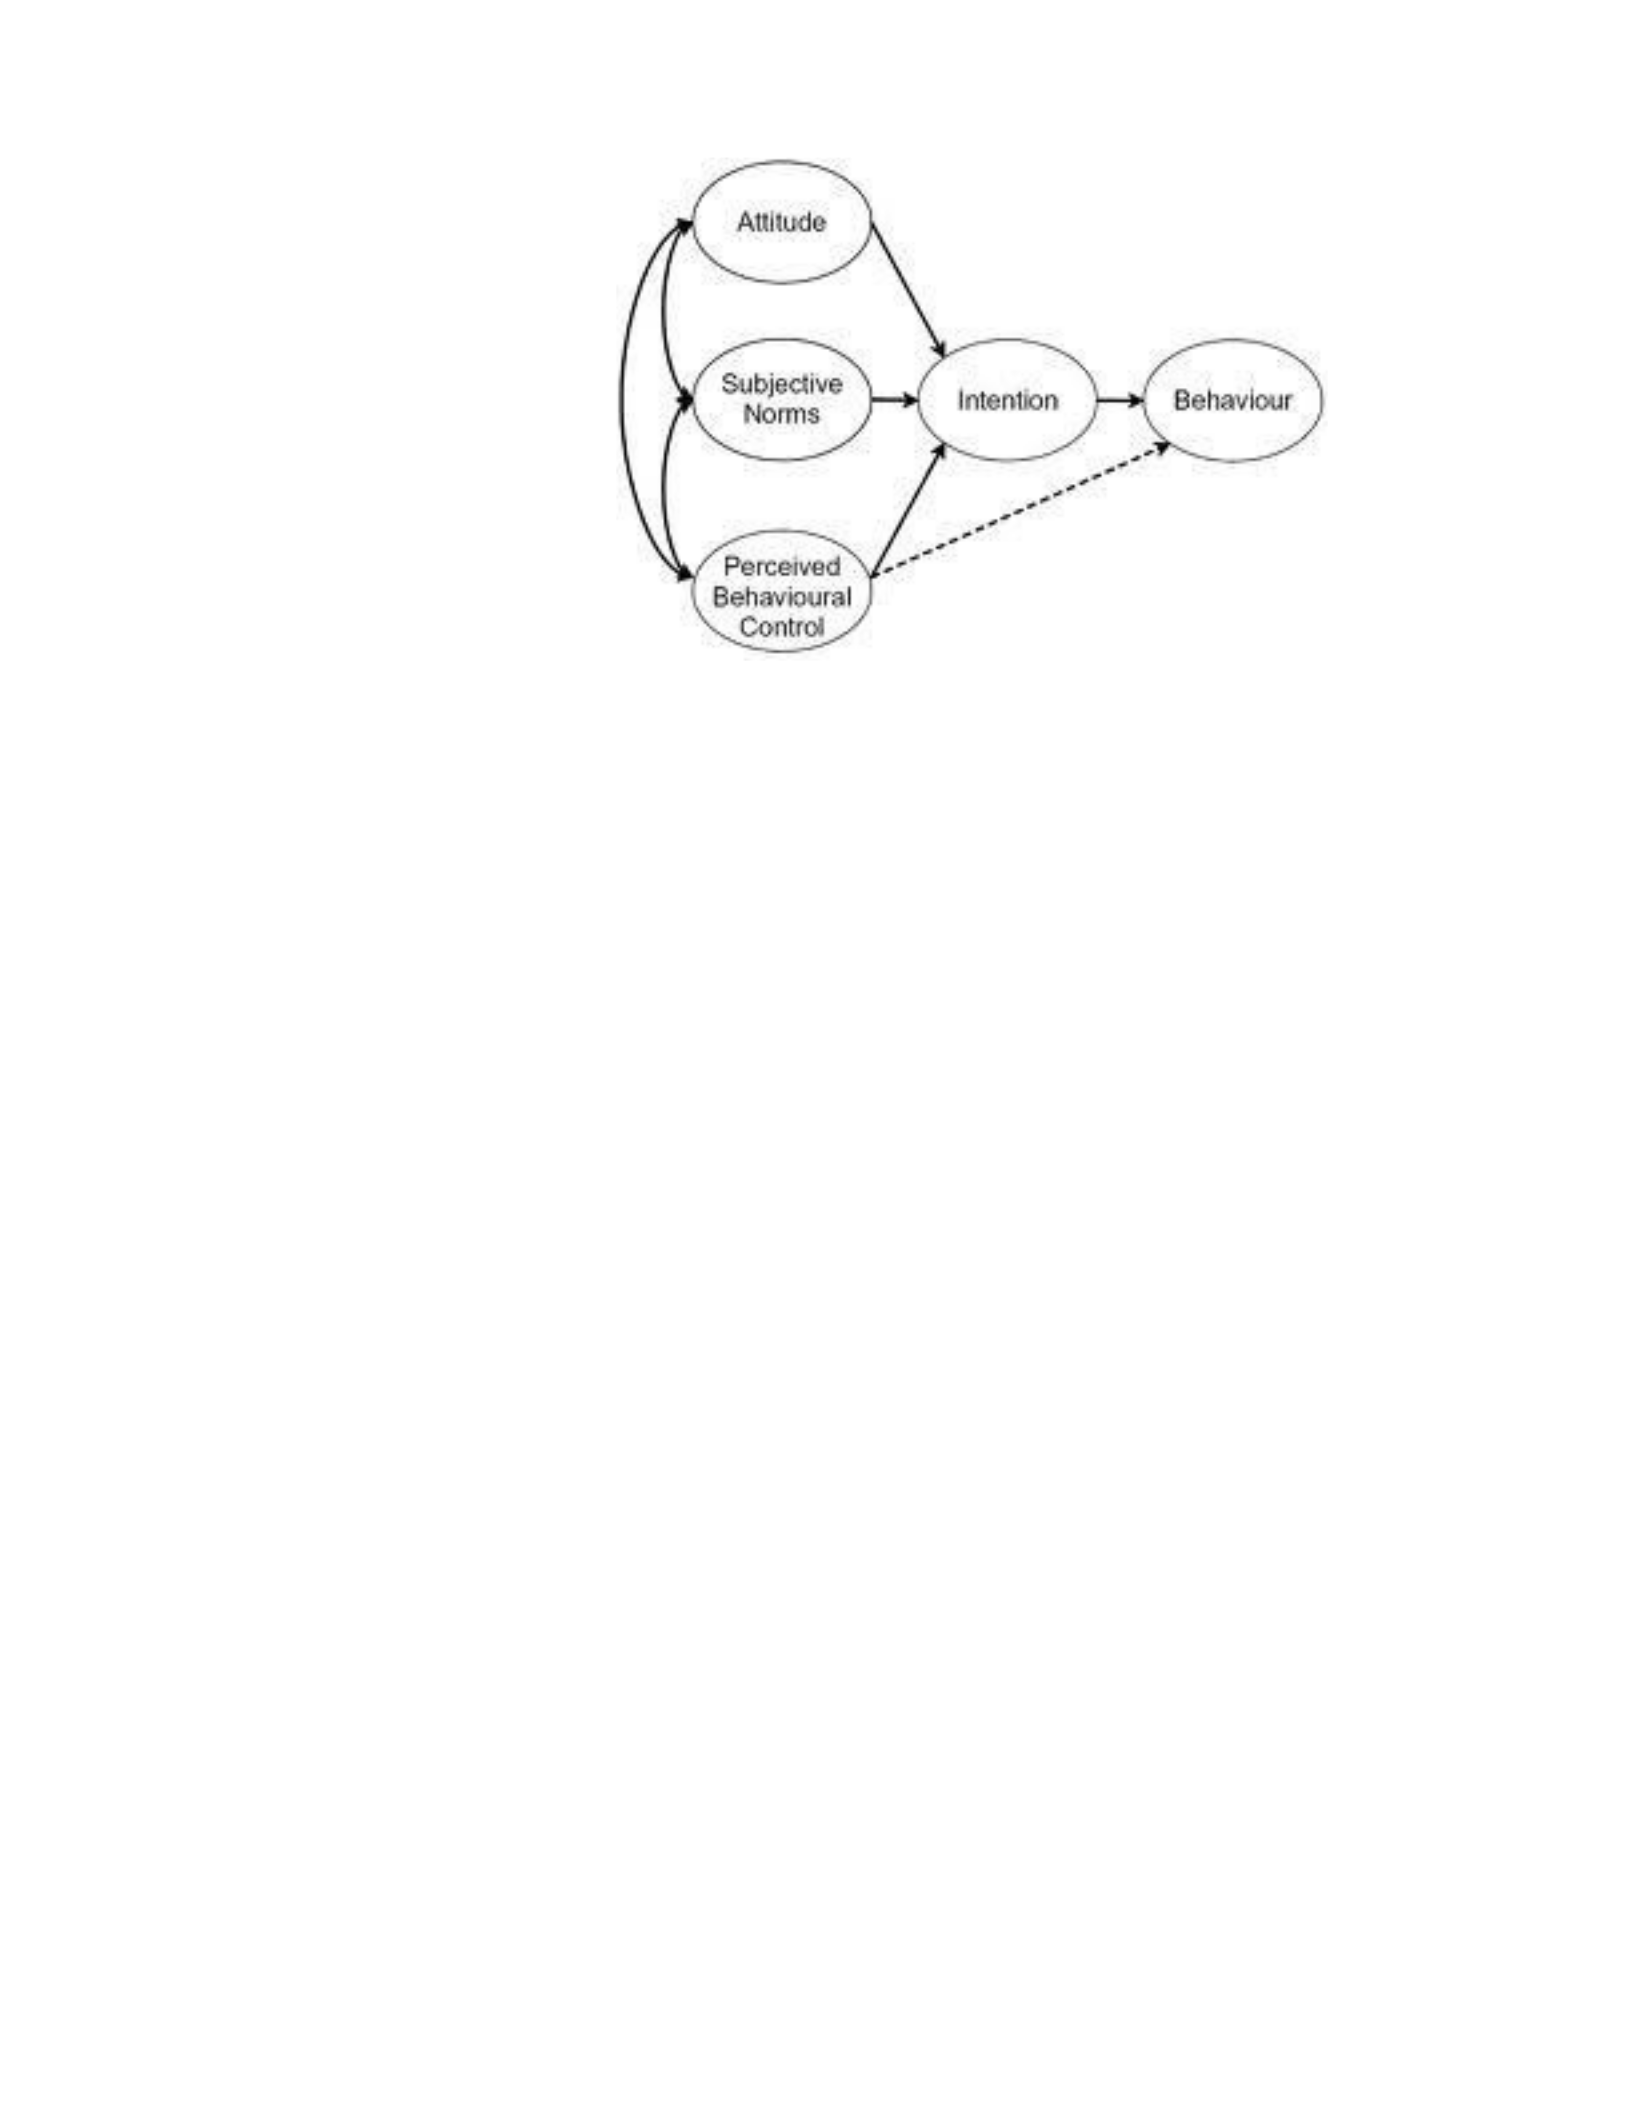
Figure 1. A conceptual model of the theory of planned behavior. Adapted from “The Theory of
Planned Behavior,” by I. Ajzen, 1991, Organizational Behavior and Human Decision Processes,
50, 179-211, p. 182.
36
Figure 2. A CONSORT diagram of the flow of participants in the randomized experiment
Agreed to participate (n = 420)
Randomized to a group (n = 271)
Sexual Negotiation
(n = 135)
Comparison Group
(n = 136)
Month 1 Post-
test (n = 122)
Month 1 Post-
test (n = 121)
* 15 failed to complete post-test
declined to 149
participate
* 13 failed to complete post-test
excluded (inclusion criteria)27
* 27 not sexually active
excluded (inclusion criteria)33
* 32 not sexually active
* 1 not 18-30 yrs. old
Analyzed
(n = 89)
Analyzed
(n = 94)

38
Table 1
Bivariate Correlation Table for Total Sample (n=183)
Variable 1 2 3 4 5 6 7 8 9 10 11 12
1. Condom use pre-test --
2. Condom use post-test 0.70** --
3. Condom use self-efficacy at pre-test 0.17* 0.07 --
4. Condom use self-efficacy at post-test 0.20** 0.19*
0.60** --
5. Knowledge of PSH at pre-test -0.02 -0.05
0.19** 0.20** --
6. Knowledge of PSH at post-test -0.05 -0.03 0.13 0.20** 0.70** --
7. Communication at pre-test -0.07 -0.07 0.01 0.14 0.12 0.14 --
8. Commitment at pre-test -0.03 -0.08 0.13 0.23* 0.18* 0.26** 0.27** --
9. Relationship satisfaction at pre-test 0.07 -0.21* 0.22* 0.33*
0.37**
0.27** 0.16 0.54**
--
10. Trust at pre-test 0.14 -0.05 0.22* 0.35** 0.38** 0.30** 0.16 0.33** 0.67** --
11. Intentions- condom use at post-test -0.64** -0.72** -0.13 -0.15* 0.09 0.08 0.11 0.10 0.09 -0.41 --
12. Intentions- knowledge of PSH at post-test -0.25** -0.24* -0.10 -0.09 -0.09 -0.06 0.04 0.21* 0.22* 0.00 0.41** --
Note. PSH = partner sexual history
*p < 0.05. ** p < 0.01.

39

Table 2
Percentage of Participants in the Treatment and Comparison Condition by Demographics
Variable Treatment Comparison Total (n)
Gender
Female
82% (73)
83% (78)
151
Male
18% (16) 17% (16) 32
Race non-Hispanic White
66% (59)
69% (65)
124
African American 11% (10) 13% (12) 22
Hispanic 22% (19) 13% (12) 31
Asian/Pacific Islander 1% (1) 3% (3) 4
Other
0% (0) 2% (2) 2
Age
18-20
63% (56)
66% (62)
118
21-25 35% (31) 29% (27) 58
25-30 2% (2) 5% (5) 7
Relationship Status
Single
35% (31)
35% (33)
64
Dating
65% (58)
65% (61)
119
Total (N) 89 94 183

40
Table 3
Summary of Reported Sexual Activity and Testing Status
Behavior Response Percentage
Hookups within 12 month (n = 64)
0
8% (5)
1 22% (14)
2 17% (11)
3 20% (13)
4 or More 33% (21)
STI Testing History (n = 177)
Tested
63% (112)
Never Tested
37% (65)
STI Testing History- in Current Relationship (n = 104)
Never Tested 32% (33)
Before sex w/ current partner 13% (14)
After sex w/ current partner 35% (36)
After last relationship ended 7% (7)
Don't know 13% (14)
41

Table 4
Summary of Descriptives for Treatment Effects on Sexual Risk Outcomes
Dependent Variables Condition
Condom use Tx
Pre-test 86 6.84 3.53 [6.10, 7.59]
Post-test 86 7.98 4.06 [7.12, 8.84]
Comparison
Pre-test 84 6.75 3.45 [5.99, 7.51]
Post-test 84 6.82 4.04 [5.95, 7.70]
Knowledge of PSH Tx
Pre-test 84 50.13 11.48 [47.67, 52.60]
Post-test 84 51.39 12.07 [48.74, 54.10]
Comparison
Pre-test 84 53.43 11.35 [50.89, 55.97]
Post-test 84 51.84 12.60 [49.10, 54.58]
Condom Use Self-Efficacy Tx
Pre-test 86 29.80 4.07 [28.94, 30.67]a
Post-test 86 31.19 4.43 [30.19, 32.18]a
Comparison
Pre-test 82 29.73 4.05 [28.85, 30.61]a
Post-test 82 30.38 4.94 [29.36, 31.40]a
Note. CI = confidence interval; Tx = treatment condition; PSH = partner sexual history.
aCI corrected for sphericity assumption violation using MANOVA analysis.
42
n M SD 95% CI

43

MS F p
Repeated Measures ANOVA for Condom Use partial η2
Table 5
Between groups
Condition 1.00 32.80 32.80 1.35 0.25 0.01
Error 168.00 4093.8 24.37
Within groups
Time 1.00 31.16 31.16 7.21 0.01 0.04
Time x Condition 1.00 24.24 24.24 5.61 0.02* 0.03
Error 168.00 725.95 4.32
Note. *p < 0.05.
44
Source df SS
MS F p
Table 6
Repeated Measures ANOVA for Knowledge of PSH
Source df SS partial η2
Between groups
Condition 1.00 285.04 285.04 1.19 0.28 0.01
Error 161.00 38606.19 239.79
Within groups
Time 1.00 2.26 2.26 0.05 0.82 0.00
Time x Condition 1.00 166.14 166.14 3.91 0.05* 0.02
Error 161.00 6849.64 42.54
Note. *p = 0.05.
45

MS F p
Table 7
Repeated Measures ANOVA for Condom Use Self-Efficacy
Source df SS partial η2
Between groups
Condition 1.00 16.20 16.20 0.53 0.47 0.00
Error 166.00 5088.5 30.65
Within groups
Time 1.00 86.50 86.50 11.1 0.00 0.06
Time x Condition 1.00 11.41 11.41 1.46 0.23 0.01
Error 166.00 1293.54 7.79
46

MS F p
47

Table 8
Summary of Descriptive Statistics for Experimental Study by Gender.
Variable by Gender Men Women
Range M SD Range M SD
Condom use at pre-test 2-12 8.53 3.37 2-12 6.51 3.43
Condom use at post-test 2-12 7.97 4.18 2-12 7.31 4.04
Knowledge o PSH at pre-test 16-60 51.94 11.84 15-60 51.29 11.97
Knowledge o PSH at post-test 27-60 52.92 11.31 14-60 51.45 12.45
Condom use self-efficacy at pre-test 23-35 31.86 3.00 15-35 29.39 4.08
Condom use self-efficacy at post-test 17-35 32.30 4.79 16-35 30.41 4.74
Intentions-condom use at pre-test 3-21 6.63 4.99 3-21 9.35 6.84
Intentions-condom use at post-test 3-21 7.40 5.94 3-21 9.41 6.65
Intentions- knowledge of PSH at pre-test 3-12 7.28 3.10 3-12 7.18 3.30
Intentions- knowledge of PSH at post-test 3-12 6.00 3.03 3-12 6.73 2.98
Relationship satisfaction at pre-test 16-25 21.53 2.37 11-25 20.74 2.81
Trust at pre-test 36-56 48.39 5.80 19-56 48.19 7.23
Commitment at pre-test 12-20 16.16 2.50 9-20 15.76 3.04
Communication at pre-test 12-24 19.95 3.63 11-24 20.64 3.31
Note. PSH = partner sexual history.
48
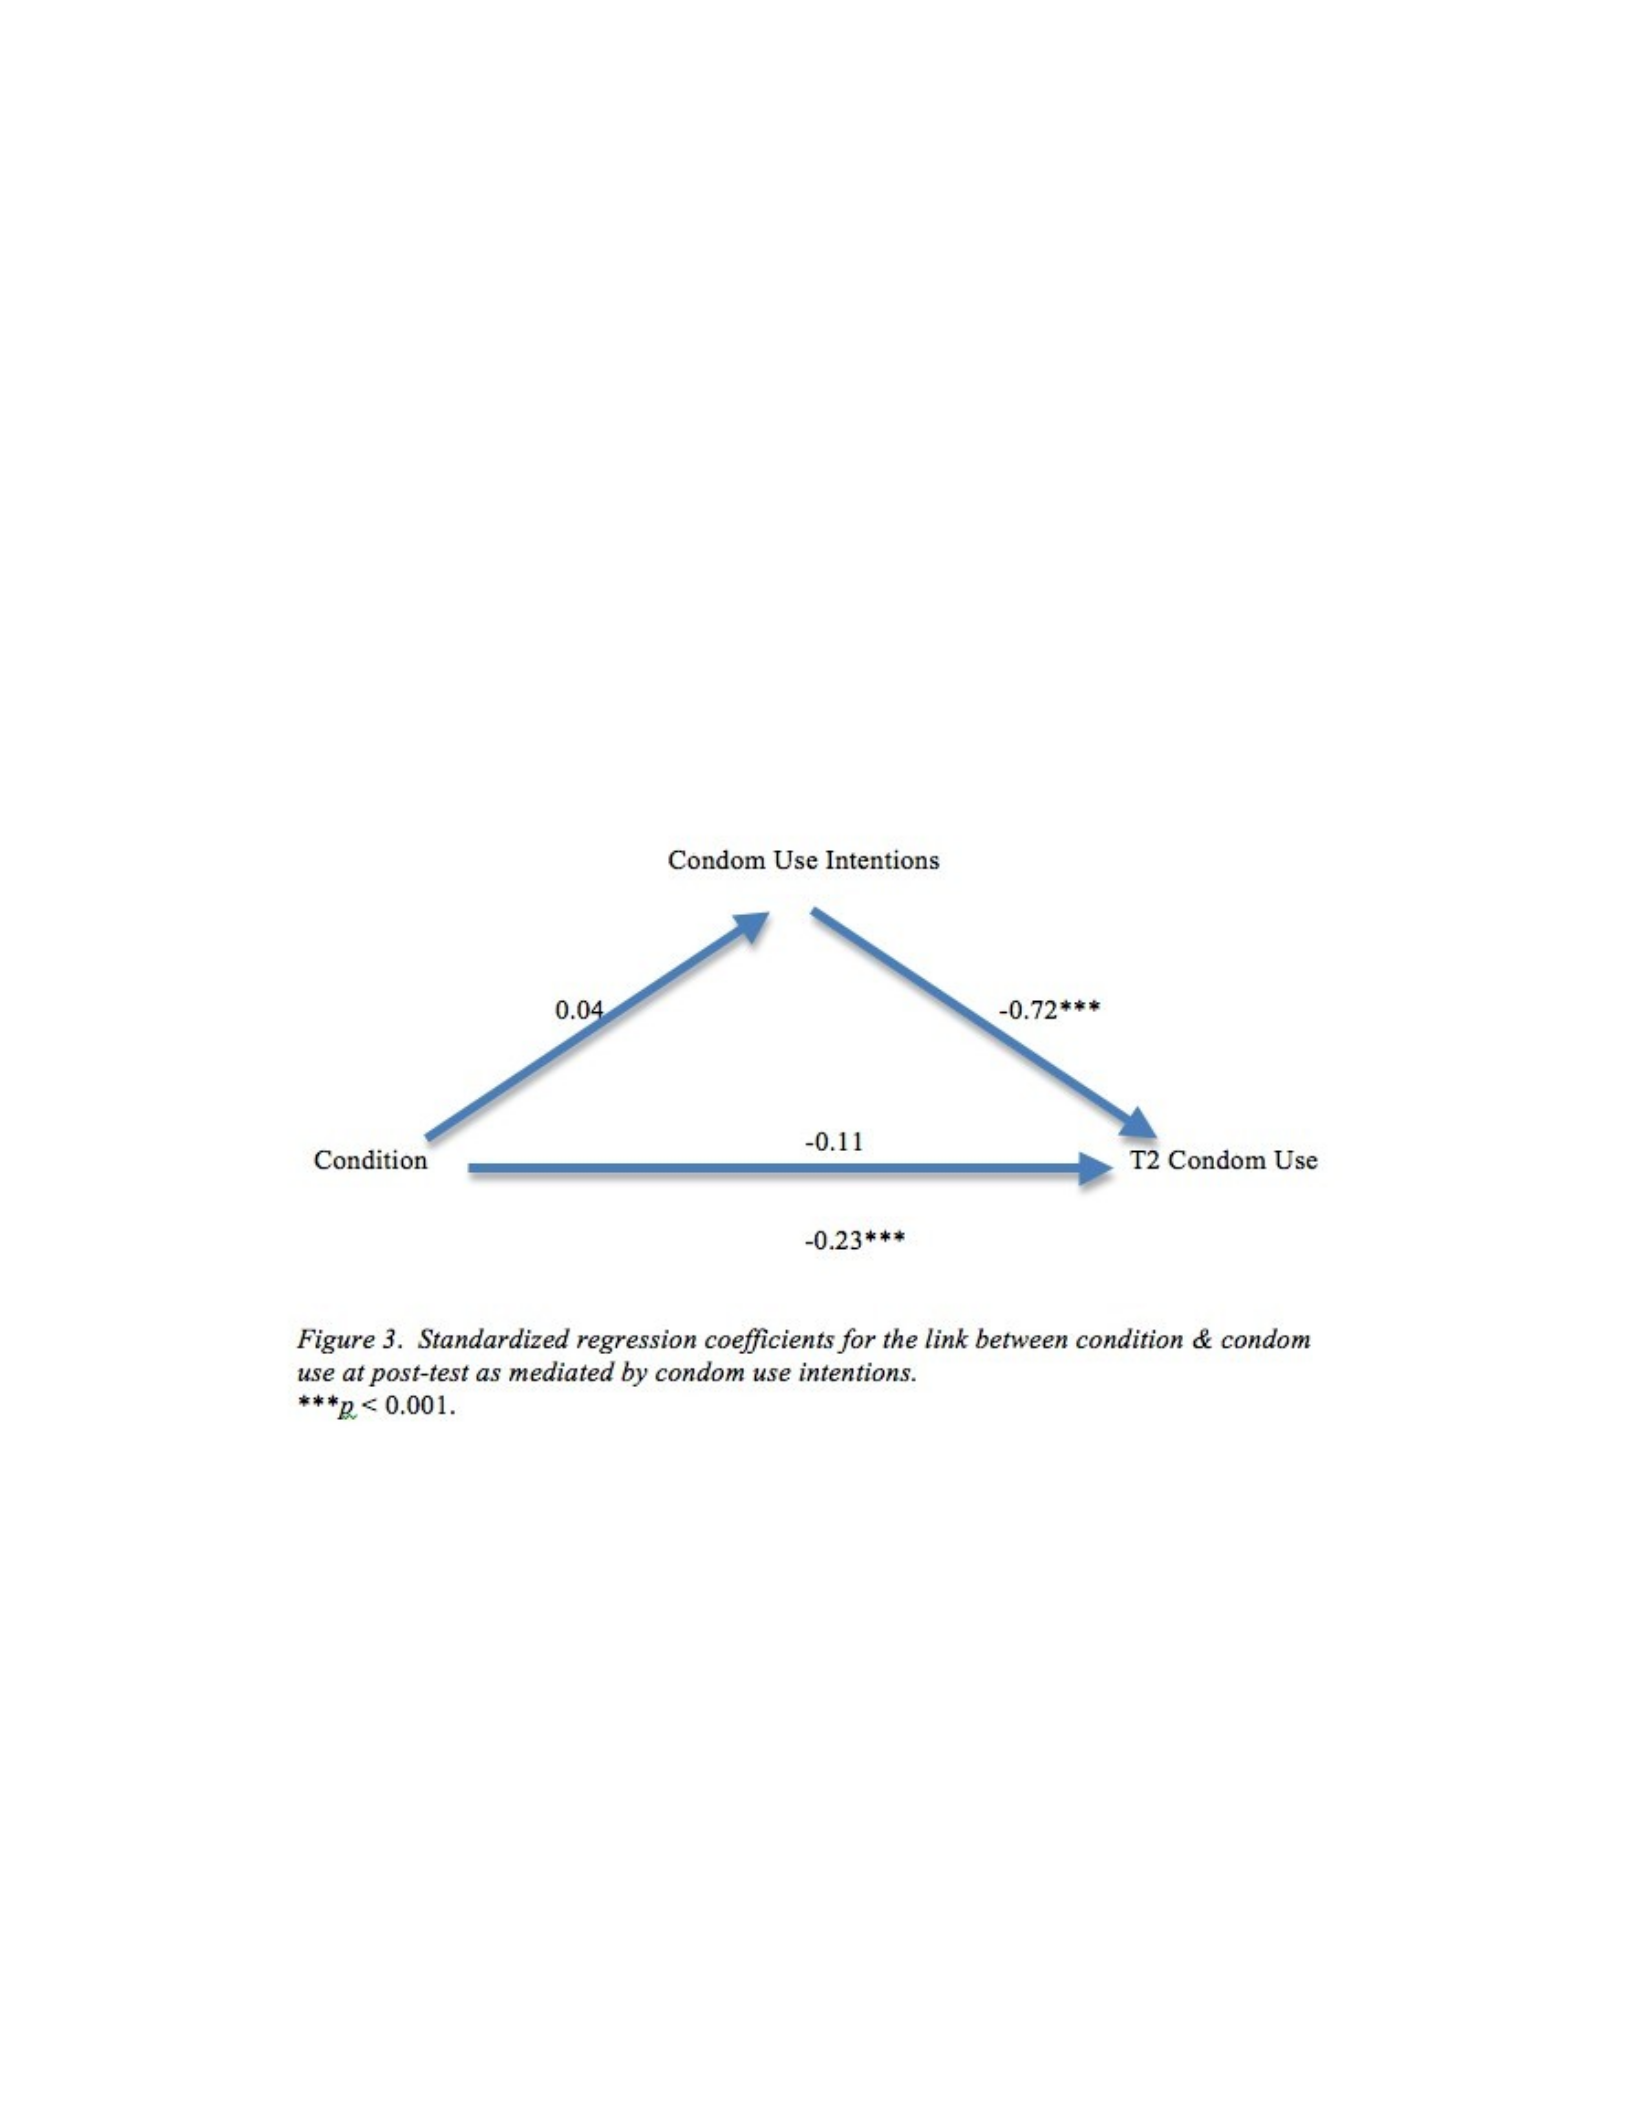
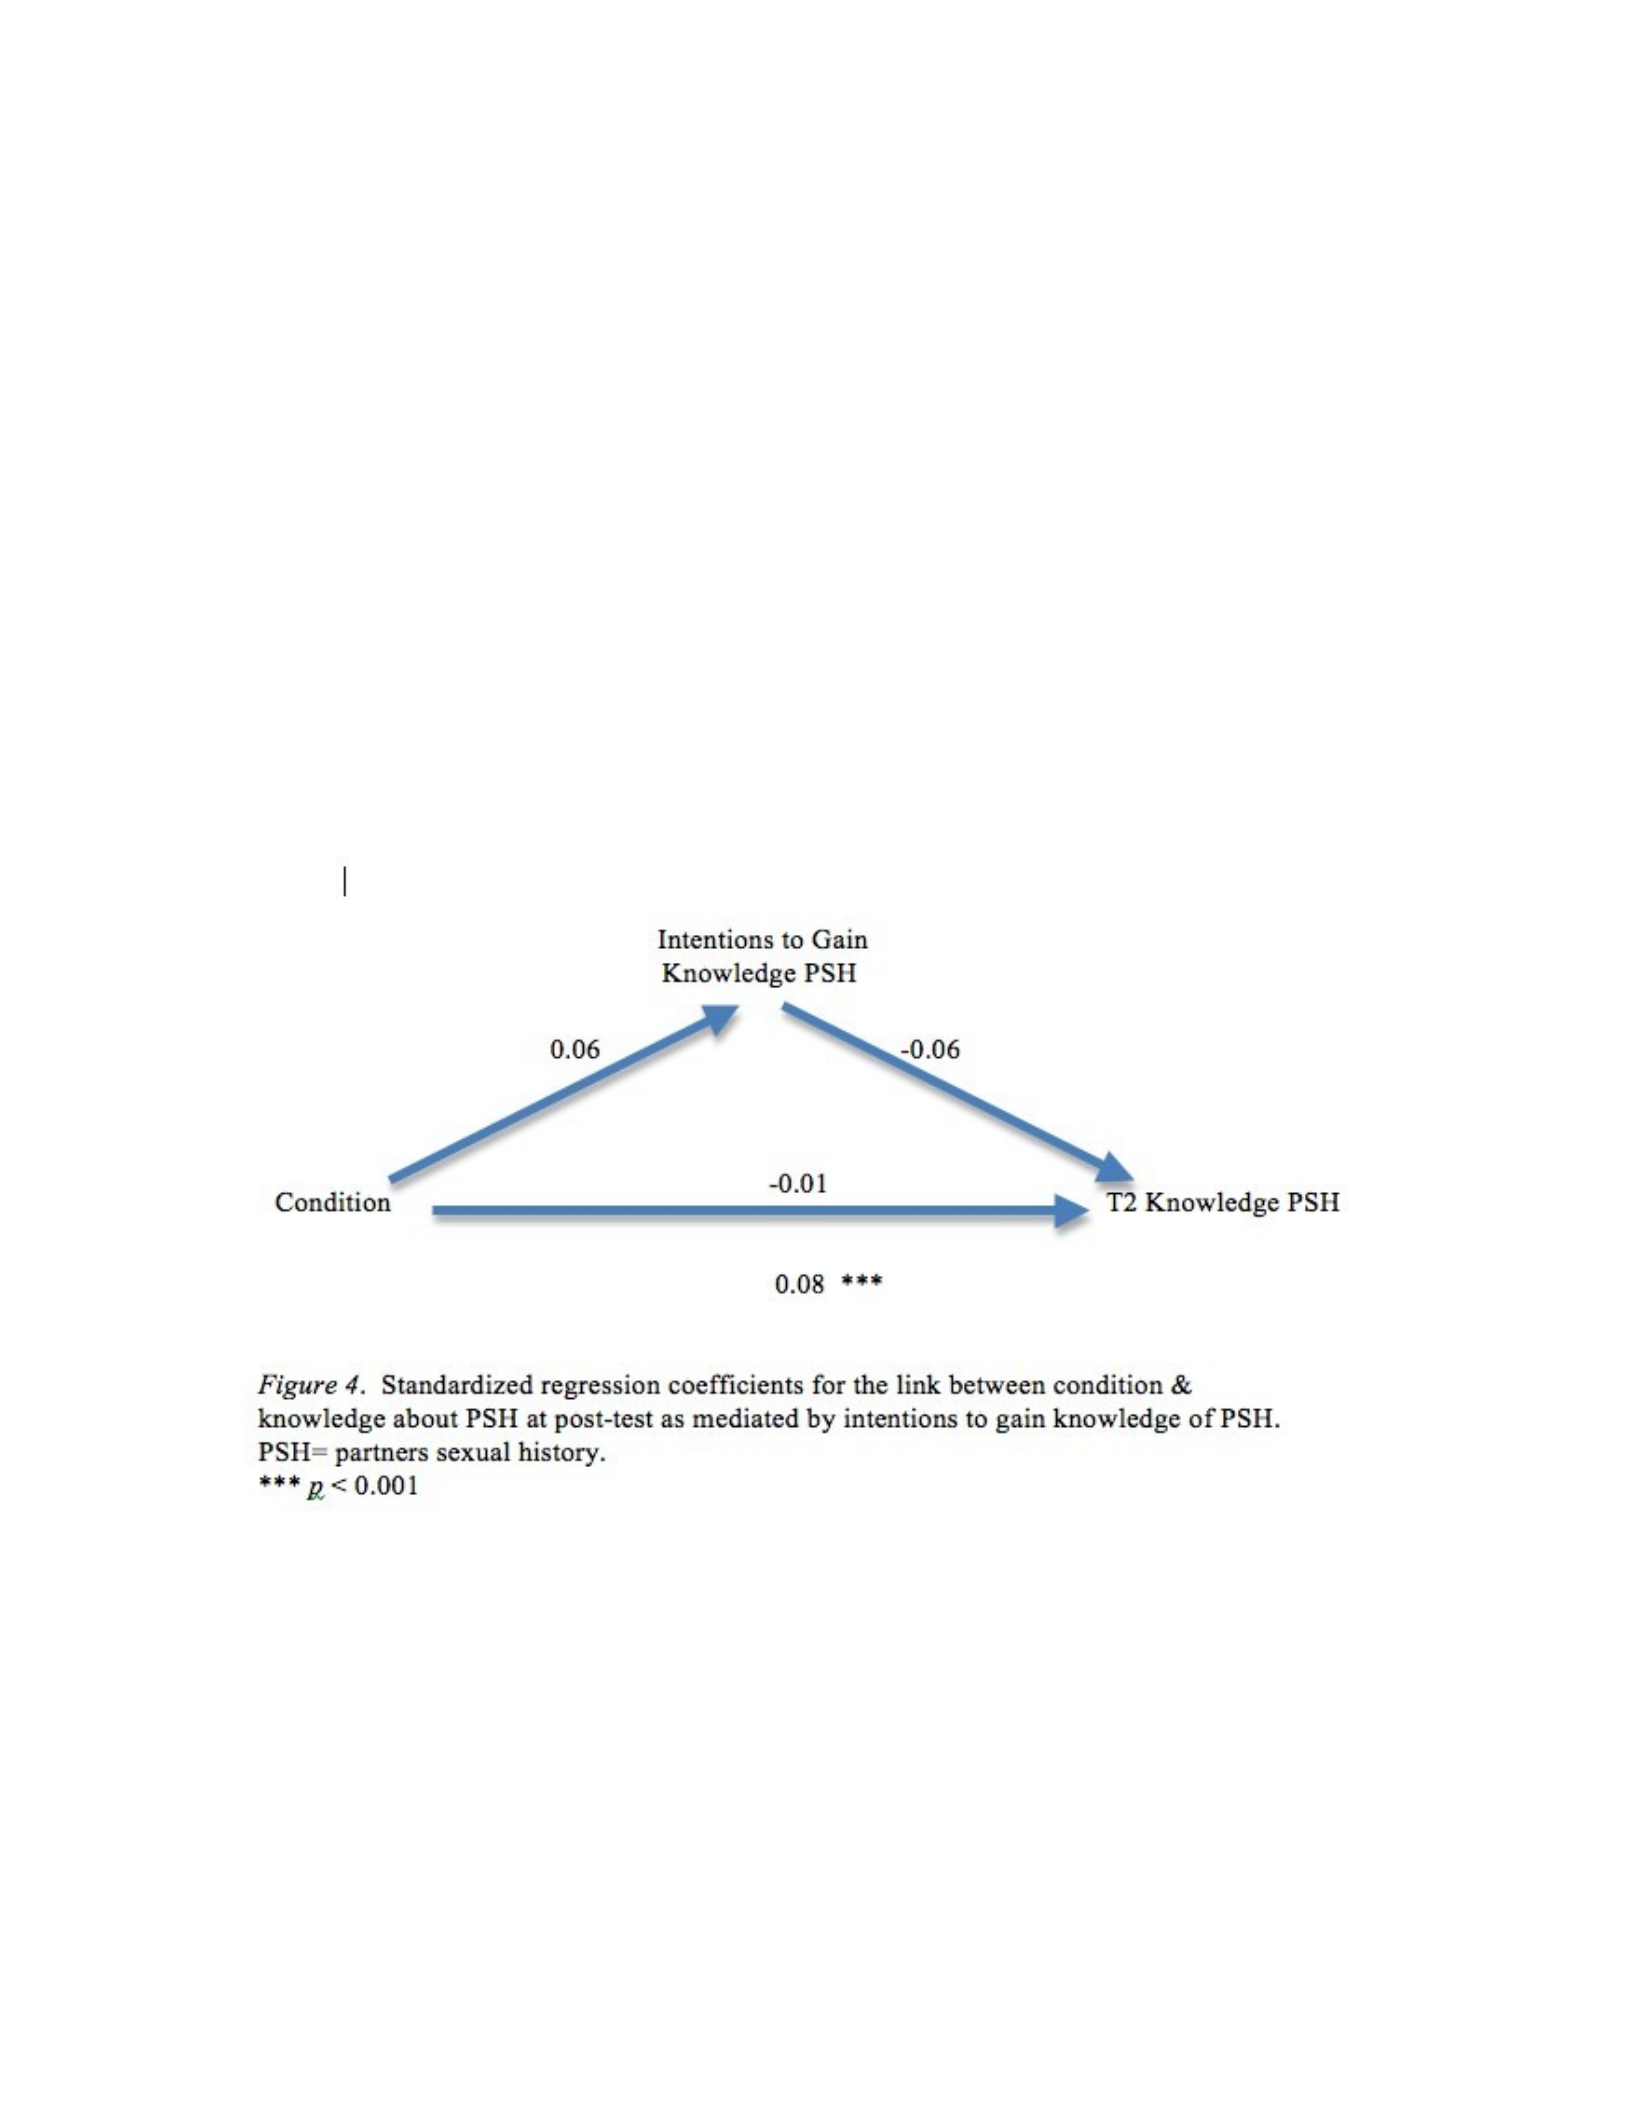
47
50


Table 9
Summary of General Linear Models Analysis for Link Between Relationship Factors
on Condom Use Among those in Exclusive Relationships (n =108)
Predictor B SE B β
Condition -1.39 0.59 -0.17*
Pre-test condom use 0 .77 0.09 0.65***
Relationship satisfaction -0.41 0.16 -0.28**
Trust 0.20 0.06 0.03
Commitment 0.17 0.12 0.13
Communication -0.06 0.09 -0.05
R2
0.49
F 16.35
Note. *p < 0.05. ** p < 0.01. ***p < 0.001.
52

APPENDIX A
Office of the Vice President For Research
Human Subjects Committee
Tallahassee, Florida 32306-2742
*** · FAX ***
APPROVAL MEMORANDUM
Date: 2/10/2012
To: Sesen Negash
Address: ***
Dept.: FAMILY & CHILD SCIENCE
From: Thomas L. Jacobson, Chair
Re: Use of Human Subjects in Research
Do relationship processes influence sexual health promotion?
The application that you submitted to this office in regard to the use of human subjects in the
research proposal referenced above has been reviewed by the Human Subjects Committee at its
meeting on 12/14/2011. Your project was approved by the Committee.
The Human Subjects Committee has not evaluated your proposal for scientific merit, except to
weigh the risk to the human participants and the aspects of the proposal related to potential risk
and benefit. This approval does not replace any departmental or other approvals, which may be
required.
If you submitted a proposed consent form with your application, the approved stamped consent
form is attached to this approval notice. Only the stamped version of the consent form may be
used in recruiting research subjects.
If the project has not been completed by 12/12/2012 you must request a renewal of approval for
continuation of the project. As a courtesy, a renewal notice will be sent to you prior to your
53

expiration date; however, it is your responsibility as the Principal Investigator to timely request
renewal of your approval from the Committee.
You are advised that any change in protocol for this project must be reviewed and approved by
the Committee prior to implementation of the proposed change in the protocol. A protocol
change/amendment form is required to be submitted for approval by the Committee. In addition,
federal regulations require that the Principal Investigator promptly report, in writing any
unanticipated problems or adverse events involving risks to research subjects or others.
By copy of this memorandum, the Chair of your department and/or your major professor is
reminded that he/she is responsible for being informed concerning research projects involving
human subjects in the department, and should review protocols as often as needed to insure that
the project is being conducted in compliance with our institution and with DHHS regulations.
This institution has an Assurance on file with the Office for Human Research Protection. The
Assurance Number is FWA00000168/IRB number IRB00000446.
Cc: Frank Fincham, Advisor
HSC No. 2011.7418
54

