


1
Section 1: The Foundation of the Study
One of the key goals of the U.S. healthcare system is to provide quality care. This can be
successful if medical and other personnel including health care administrators collaborate on
various levels to assimilate complex medical information (Nimkar, 2016). The efficient use of
information technology has enabled the assimilation of information from various sources in
health care. Nimkar (2016) stated that health information technology consists of a wide range of
applications in educational, administrative, clinical and research areas of healthcare. Health
information technology (HIT) involves the exchange of health information via an electronic
environment (Health Information, 2019). HIT utilization in the health care industry has been
found to improve the quality of health care, prevent medical errors, decrease paperwork, increase
administrative efficiencies, and expand access to affordable health care (Health Information,
2019). The following major applications namely, electronic health records, Electronic personal
records system, IT health education, health and the use of social media have led to a better
coordination of healthcare delivery (Nimkar, 2016). While health information technology offers
good benefits, there are a number of challenges it poses. The primary objective of this paper was
to explore and understand the use and management of health information technology from the
positive and negative perspective through the review of professional literature, interviews, and a
single case study, thereby, gain a clear direction on the extent of the problems which it poses
pertaining to the disruption of quality care delivery, resulting in the impact on the organization’s
business reputation. Furthermore, understand the benefits which could be realized with its
efficient utilization.

2
Background of the Problem
The healthcare system in the United States has faced some monumental challenges in
recent years. These challenges have been the result of changing population demographics and
their state of health (Daim et al., 2016). Increases in chronic illnesses have led to increased
hospitalizations and transitions between providers and some settings in the healthcare system
resulting in harmful and inadequate information transfer which have hampered the reconciliation
of treatment plans (Daim et al., 2016). These issues and challenges have urgently called for
solutions to combat the risks and improvement in healthcare delivery system. One solution to the
problem has been the harnessing of health information technology.
Health information technology involves the exchange of health care information via an
electronic environment (Health Information, 2019). Health information technology utilization in
the healthcare industry has been found to improve the quality of health care delivery, prevention
of medical errors, decrease paperwork, increase administrative efficiencies, and expansion of
access to affordable health care (Health Information, 2019). According to Buntin et al. (2011),
utilization of health information technology can also result in cost savings and greater
engagement by patients in their personal health care. Contemporary technology has been
evolving at an unparalleled rate, so quickly that users find it difficult to keep pace and quantify
its value or assess its effectiveness. As technology continues to be an integral part of health care,
administrators need to continually devise strategies to implement or incorporate its use into daily
operations to help improve the quality of care and reduce costs.
Sittig et al. (2018) stated that health information technology still requires substantial
improvements in order to offer reliable and efficient use for patient care. Examining the issues
related to health information technology management thoroughly show that safe effective design,

3
development, and its use requires a shared responsibility and focus on the people, processes,
environment, and the technology involved (Sittig et al., 2016). Palojoki et al. (2017) agreed that
health information technology such as electronic health records offer benefits that include
improved health care, reduced clinicians’ workloads, cost effectiveness and error reduction.
However, the use of this type of technology can also pose new risks related to safety since they
tend to disrupt the traditional norms of the clinicians. Because of that, there is a need for more
information regarding the efficient use of electronic health records to prevent the risks (Palojoki
et al., 2017). Some of the techniques suggested by Palojoki et al. (2017) included developing
methods of supporting user awareness as well as monitoring and managing.
It is clear that the widespread adoption of health care information technology brings
many potential benefits to health care (Sittig et al., 2020). At the same time, problems with
mismanagement can disrupt the delivery of care and increase the likelihood of new and often
unforeseen errors that affect the safety and quality of clinical care and may lead to patient harm
(Kim et al., 2017). For organizations to be successful and benefit from health information
technology, it is important that they understand what causes the mismanagement issues as well
as how and why mismanagement of health care information technology could result in problems
that can disrupt care delivery and pose threats to patient safety. With this understanding,
healthcare organizations can device steps of dealing with these issues effectively for the sound
business practices.
Problem Statement
The general problem discussed was that the mismanagement of health information
technology disrupts health care delivery resulting in medical errors which could negatively
impact the firm’s business reputation. Sittig et al. (2020) stated that if health information

4
technology is not designed, developed, implemented, and managed appropriately, it disrupts
health care delivery and creates safety issues that impact healthcare organizations in delivering
quality care. According to Palojoki et al. (2017), health information technology such as
Electronic Health Records (EHR) pose the risk of errors arising from inadequate information
needed to support user awareness, lack of monitoring and efficient management resulting in the
disruption of safe health care delivery. Kim et al. (2017) stated that if not well managed, health
information technology in fully digitalized health care organizations can disrupt the delivery of
health care and result in threats of safety and harm to the patients. The specific problem
addressed is that the potential mismanagement of health information technology disrupts health
care delivery resulting in delivery of quality care which affects the firm’s business reputation in
Lancaster Pennsylvania within the Penn Medicine Lancaster General Hospital (LGH).
Purpose Statement
The purpose of this qualitative single case study was to identify and discuss current issues
surrounding the inefficient management of health information technology as they affect the
delivery of quality health care, resulting negative impact on the organization’s business
reputation (Gauthier et al., 2018). The researcher sought to assess what steps health care
organization leaders have taken to mitigate this problem in the past, present, and how they plan
to continue in the future. The findings of this study could assist health care organizations with
the efficient management of health information technology, thereby, result in quality care
delivery leading to good a business reputation.
Research Questions
The researcher asked the following research questions to effectively discuss and address
the problem as mentioned above and derive a suitable conclusion.

5
RQ1: How has the mismanagement of health information technology within health care
organizations led to medical errors which resulted in the disruption of healthcare delivery?
This question sought to understand how the inefficient management of health information
technology has led to medical errors resulting in the disruption of quality healthcare delivery.
While health information technology can provide beneficial quality care delivery, if not managed
efficiently, it can result in more new errors that can impact patient safety and quality care
delivery (Kim et al., 2017).
RQ1a: What are the Electronic Health Records management issues that contribute to
medical errors?
This sub question specifically inquired how the mismanagement of health information
technology with the focus on EHR has resulted in medical errors impacting the delivery of
quality care. It has been shown that while EHR have contributed to the improvement of
coordination and improvement of healthcare, it can also pose some risks to the patient stemming
from its inefficient design and implementation; inadequate information to support user
awareness; lack of monitoring and efficient management (Palojoki et al., 2017).
RQ2: Why has the mismanagement of health information technology negatively
impacted patient safety and resulted in the disruption of efficient delivery of health care?
The purpose of this research question was to understand why the mismanagement of
health information technology has negatively impacted patient safety, resulting in the disruption
of efficient health care delivery. According to Kim et al. (2017), not managing health
information technology efficiently impacts the clinical decisions and care process offered by the
healthcare organization and results in outcomes which can potentially harm the patient due to
clinical errors.

6
RQ3: How has the mismanagement of health information technology within health care
organizations led to the disruption of quality health care delivery resulting in medical errors and
negatively impacting business reputation?
This question sought to understand how the mismanagement of health information
technology within the health care system has led to the disruption of quality health care delivery,
resulting in medical errors, and impacting the organization’s business reputation. Management
issues arising from health information technology are due to the reason that it is not designed,
implemented, monitored, and managed efficiently to ensure the safety of the patient and
provision of quality care resulting in potential negative impact on the firm’s business reputation
and return on investment (Sittig et al., 2020).
Nature of the Study
The purpose of this section of the paper is to explain the methodology that was used to
conduct a study on current management issues in the health care information technology as
relates to patient safety related to medical errors resulting in a negative impact on the firm’s
business reputation. Outlining the methodology that was used is necessary because in research,
there is a need to consider and explain the appropriate method applicable to the phenomenon
being investigated in order to discover and understand it (Creswell & Poth, 2018). The method
for this study was qualitative analysis. Data collection was derived from the review of literature
on case studies dealing with the subject matter, themes derived from the literature review based
on the problem statement, research questions and interviews were used to formulate the data.
Discussion of Research Paradigms
Haigh and Withell (2020) described research paradigm as follows: First, what a
researcher believes about the nature of what they can know about it. Second, the likely influence

7
of existing ideas and values on what they want to know, how they want to know, and the criteria
used to make the judgement about the knowledge and the right strategies for evaluation.
According to Creswell and Poth (2018), there are four primary paradigms that can be applied by
a researcher. They are positivism, post-positivism, constructivism, and pragmatism. Positivism
paradigm has a researcher view an inquiry as a single reality that one seeks to discover and is
commonly associated with quantitative research. Post-positivism paradigm has a researcher view
an inquiry as a series of logically related steps in multiple perspectives and it is believed to be
providing an alternative to the positivism approach. Constructivism paradigm has a researcher
view that multiple realities are constructed through once lived experiences and interaction with
others (Creswell & Poth, 2018). Pragmatism views that reality is useful, practical and works. In
other words, it looks at issues from a practical standpoint and applies problem solving skills
(Creswell & Poth, 2018).
In this study, the researcher’s paradigm was pragmatism because it assists in
understanding the real-world view issues that needed to be addressed and view them from a
practical standpoint in solving them. Pragmatism looks at issues from a practical point of view
and applies problem solving skills (Kaushik & Walsh, 2019). Understanding the connection
between philosophical worldview and research methodology assist in recognizing the issues that
need to be addressed, the causes and how to solve them (Kaushik & Walsh, 2019). For this study
“Current management issues in health care information technology”, the researcher needed to do
some research on how and why it occurred. Additionally, what steps were being taken to correct
these issues. Feilzer (2018) stated that pragmatism avoids issues of truth and reality, however, it
accepts philosophically that there are multiple realities which are open to empirical inquiry and
thus supports solving real world problems. It indicated that pragmatism is a suitable paradigm for

8
the problem statement on the mismanagement of health care information technology resulting in
errors that negatively impact the firm’s business reputation because this is a practical problem
currently prominent in the real world of health care information technology management and
needed an empirical study to address why it exists and what could be done to resolve it.
According to Rechberg (2018), research done using pragmatism sets the focus on the
research problem and helps to find the best responses to the research questions. Pragmatism
looks at the practical consequences which research questions seek answers in solving real
problems (Rechberg, 2018). Research questions for this study were structured to seek answers in
solving the problem.
Discussion of Method
According to Creswell and Creswell (2017), research designs are classified as
quantitative, qualitative, and mixed methods. Quantitative methods are fixed design methods
which are characterized by the following designs: experimental, quasi experimental, non-
experimental, and longitudinal. They are more suitable for a research study that requires the
analysis using quantitative tools such as statistical analysis. Qualitative methods as described by
Creswell and Poth (2018), are the flexible methods which utilize qualitative study which allow
for the flexibility of adjusting the research when necessary. They are characterized by the
following research designs: narrative, phenomenology, grounded theory, ethnography, and case
study. Lastly mixed methods are described as being convergent parallel, explanatory sequential,
exploratory sequential and complex with embedded core designs (Creswell & Poth, 2018). They
allow for the use of the combination of quantitative and qualitative methods in the research
study.

9
This study was conducted with a flexible design using qualitative methodology,
specifically a single case study design will be used. This type of design allowed the researcher to
gain more contextual and an in-depth knowledge about the specifics of management issues in
health care information technology management within the Lancaster General Hospital in
Lancaster, Pennsylvania. The qualitative research design method is an appropriate approach for
seeking the solution to the research problem stated through the research questions as well as the
employment of the case study method; since the desire of the researcher in this study sought to
understand specific issues that are causing the mismanagement of health care information
technology with regards to patient safety issues in medical errors and harm leading to the
negative business reputation of the organization. González Macias and Cuevas Contreras (2019)
stated that qualitative research explores reality just as others may experiment with it. Because of
that, it follows a path towards flexible and holistic investigation about persons, organizations or
groups that are objects or phenomenon. Thus, leading to the quality and complexity which are
the essence of what was being studied. Hence, applicable to the research question inquiring how
the mismanagement of health care information technology within health care organizations has
led to the disruption of quality care delivery resulting in medical errors and negatively impacting
the firm’s business reputation. According to Hamilton and Finley (2019), qualitative research
methods are the essential component of implementation research. Which means that they are the
study methods which use strategies to adopt and integrate evidence-based health intervention
into clinical and community environments to improve health outcomes.
The other two design methods, namely fixed methods and mixed methods did not fit into
the realm of the research which was being conducted since it is more qualitative oriented.
Creswell and Poth (2018) stated that fixed design such as quantitative research normally involves

10
systematic and empirical investigation through the use of statistics and other quantitative
methods as well as the processing of data. Mixed methods involve the use of both quantitative
and qualitative methods in research whereby the quantitative methods include the collection,
analysis, and interpretation of data in numerical forms and qualitative method are comprised of
the collection, analysis, and interpretation of narrative data (Creswell & Poth, 2018).
Discussion of the Design
The qualitative design methods include the following: narrative, phenomenology,
grounded theory, ethnography, and case study. Narrative design is the study of a phenomenon. It
is concerned with the production, interpretation, and representation of storied accounts of lived
experiences (Mills, 2000). In narrative design, researchers describe the lives of individuals,
collect stories about people’s lives and write narratives of individual experiences (Connelly &
Clandinin,1990). The stories follow a chronology of events, this chronology may be existing or
shaped by a designer. The major characteristics of a narrative design comprise of the experiences
of the individual, chronology of experiences, life stories, restorying from the filed text, coding
the field texts for themes or categories, incorporating the context or place into the story and a
collaboration between the researcher and the participant in the research study (Connelly &
Clandinin, 1990).
Phenomenological design is the common meaning derived from individual experiences.
In this design, the researcher describes lived experiences (Moustakas, 1994). Phenomenology
involves the exploration of a phenomenon for single concept or idea where researchers use a
group of individuals who have experienced the same phenomenon as participants. Because of the
objective and subjective experiences, phenomenologists should use bracketing to segment their
biases before conducting interview. Interviewing is performed until data saturation level is

11
reached. The systematic data analysis is used until significant statements are derived and
interpreted; then the meaning derived in detail, and the result becomes the essence of experience
(Moustakas, 1994). There are two primary types of phenomenological design namely:
Hermeneutical phenomenology and Transcendental phenomenology. Hermeneutical
phenomenology involves capturing lived experiences and texts of life (Van Manen, 2016).
Transcendental phenomenology involves capturing the participant’s experiences in the way it
was perceived (Moustakas, 1994). The analysis of procedures involves textural, structural and
essence of the experiences (Van Kaam, 1966.).
Grounded theory is defined as a qualitative research design which assists in generating or
discovering a theory having unified theoretical explanations (Corbin & Strauss, 2008). The
theory is grounded in data obtained from participants who have experienced the process (Strauss
& Corbin, 1998). This design includes a focus on a process or action which has distinct steps
occurring over time. Its goal is to develop a theory which explains something or how something
works. Researchers using this design use a technic called meowing, meaning a recording of ideas
through collection of data and analysis. Interviewing is the primary data collection method. In
this design, researchers constantly compare the data gleaned with new data.
Ethnography is studying a culture of a group to describe and interpret shared and learned
patterns of values, behaviors, beliefs, and language (Harris, 2001). The research is both the
process and an outcome (Agar, 1996). Ethnographic researchers focus on developing a complex
and complete description of a group culture, either a set or subset of people. The researcher will
look for regularities in behaviors requiring that a cultural group be intact enough to have
established norms. Its roots lie in cultural anthropology; with its focus on small scale societies
and the original central concept remains paramount today. In summary, that is the concern with

12
nature, construction and main. There are many forms of ethnographic designs. The two popular
types of ethnographic designs are Realist ethnography and the critical ethnography. Realist
ethnographic is the most traditional approach, and it seeks the objective account of third party
prospective. Critical ethnography involves the researcher advocating for the emancipation of a
marginalized group through their research (Thomas, 1993).
Qualitative case design refers to the studying of a case with the bounds of real-life
contemporary context or setting (Yin, 2018). However, not with a methodology but with what
must be studied (Stake, 1995). Stake (1995) stated that the identification of a specific case is
bounded by parameters such as place and time. The intent may be intrinsic or instrumental with
the goal of presenting an in-depth understanding of the case. Data analysis is a feature of case
study design which involves the study of single or multiple cases in which a description of the
case is provided along with the themes and issues or specific situations. The way the data are
presented may be chronological across cases or theoretical. The structure depends on the
research problem and case itself. Yin (2018) described case study research design as an
investigation of one or more specific instances of something that comprises cases in the study.
The author states that a case can be something more concrete like an organization, an individual,
or a group, or something more abstract as an event, a management decision or program. Yin
(2018) also defined some common features for case study as including the following features: In
depth study of several smaller cases studied in real life context and the use of multiple sources of
data including interview, observation, archival documents, and physical artifacts.
The case study method was more appropriate for the researcher’s chosen research study
because it sought to address a problem within the business environment which dealt with the
inefficient management of health information technology. As discussed above, the case study

13
deign addresses descriptive questions. A case study research design encompasses an
investigation of one or more specific instances and something more concrete like an
organization, individual and a group or something more abstract like a management decision
(Yin, 2018). Hence case study research of an organization such as Lancaster General Hospital on
the mismanagement of health information technology was suitable.
The other four methods namely: narrative, phenomenology, grounded theory, and
ethnography may have not been suitable because of the following reasons regarding each
method: First, narrative research is appropriate to use when the research is focusing on
individual’s stories or stories of a small number of individuals’ stories. These topics may discuss
concepts such as how people cope with stress, illness, or unemployment since they provide a
greater understanding of a phenomena (Creswell & Poth, 2018). Second, phenomenology design
is used when a researcher wants to describe a phenomenon such as insomnia, anger, grief or
undergoing surgery (Moustakas, 1994). It is generally and widely used in various areas of
research that deal with human experiences such as nursing, psychology, sociology, and education
(McConnell-Henry et al., 2009). Third, grounded theory is often used when the theory is not
available but is needed to explain or understand the process or existing model which has not been
tested for the population the researcher is interested in or if the data collection is incomplete. It
requires the researcher to complete interviews until data saturation has been met (Creswell &
Poth, 2018). Lastly, since ethnographic research is a process when the researcher studies an
intact cultural group in a natural setting over a period by collecting data, observations, and
interviews; it would be appropriate to use in schools, organizations, or any other phenomenon
where individuals interact daily and share a common culture (Creswell & Poth, 2018). For
instance, in a school it may be used to a school that provides privileges to certain type of students

14
and in an organization, it may study why promotion is mostly allocated based on age rather than
merit.
Summary of Nature of the Study
Pragmatism and the case study method for this qualitative research sought to address
current issues in health care information technology as they relate to patient safety which causes
medical errors resulting in a negative impact on the firm’s business are appropriate. They both
support the research study on real world view problems as they relate to functionality, accuracy,
and credibility. However, to capture the desired results for the research, it was necessary for the
researcher to craft the case study research properly, ensuring that the right research questions are
practical. Doing this resulted in the correct information that yielded the appropriate data for the
final analysis used in resolving the problem.
Conceptual Framework
The researcher created the conceptual frame of this study to illustrate how the four
elements, namely, concepts, theories, actors, and contrasts, help guide the study research as they
are related to the problem statement. The researcher first illustrated the relationship among these
elements leading to the desired outcome; second provided a discussion supported by literature on
the elements and a detailed discussion of the flow of information and the elements of the
research framework. According to Evans (2016), a conceptual framework helps organize
structures for research design, data collection, and interpretation. The researcher discussed how
the findings correlate with the elements of the research framework, thereby, guiding on the
causes of the inefficient management of health information technology.
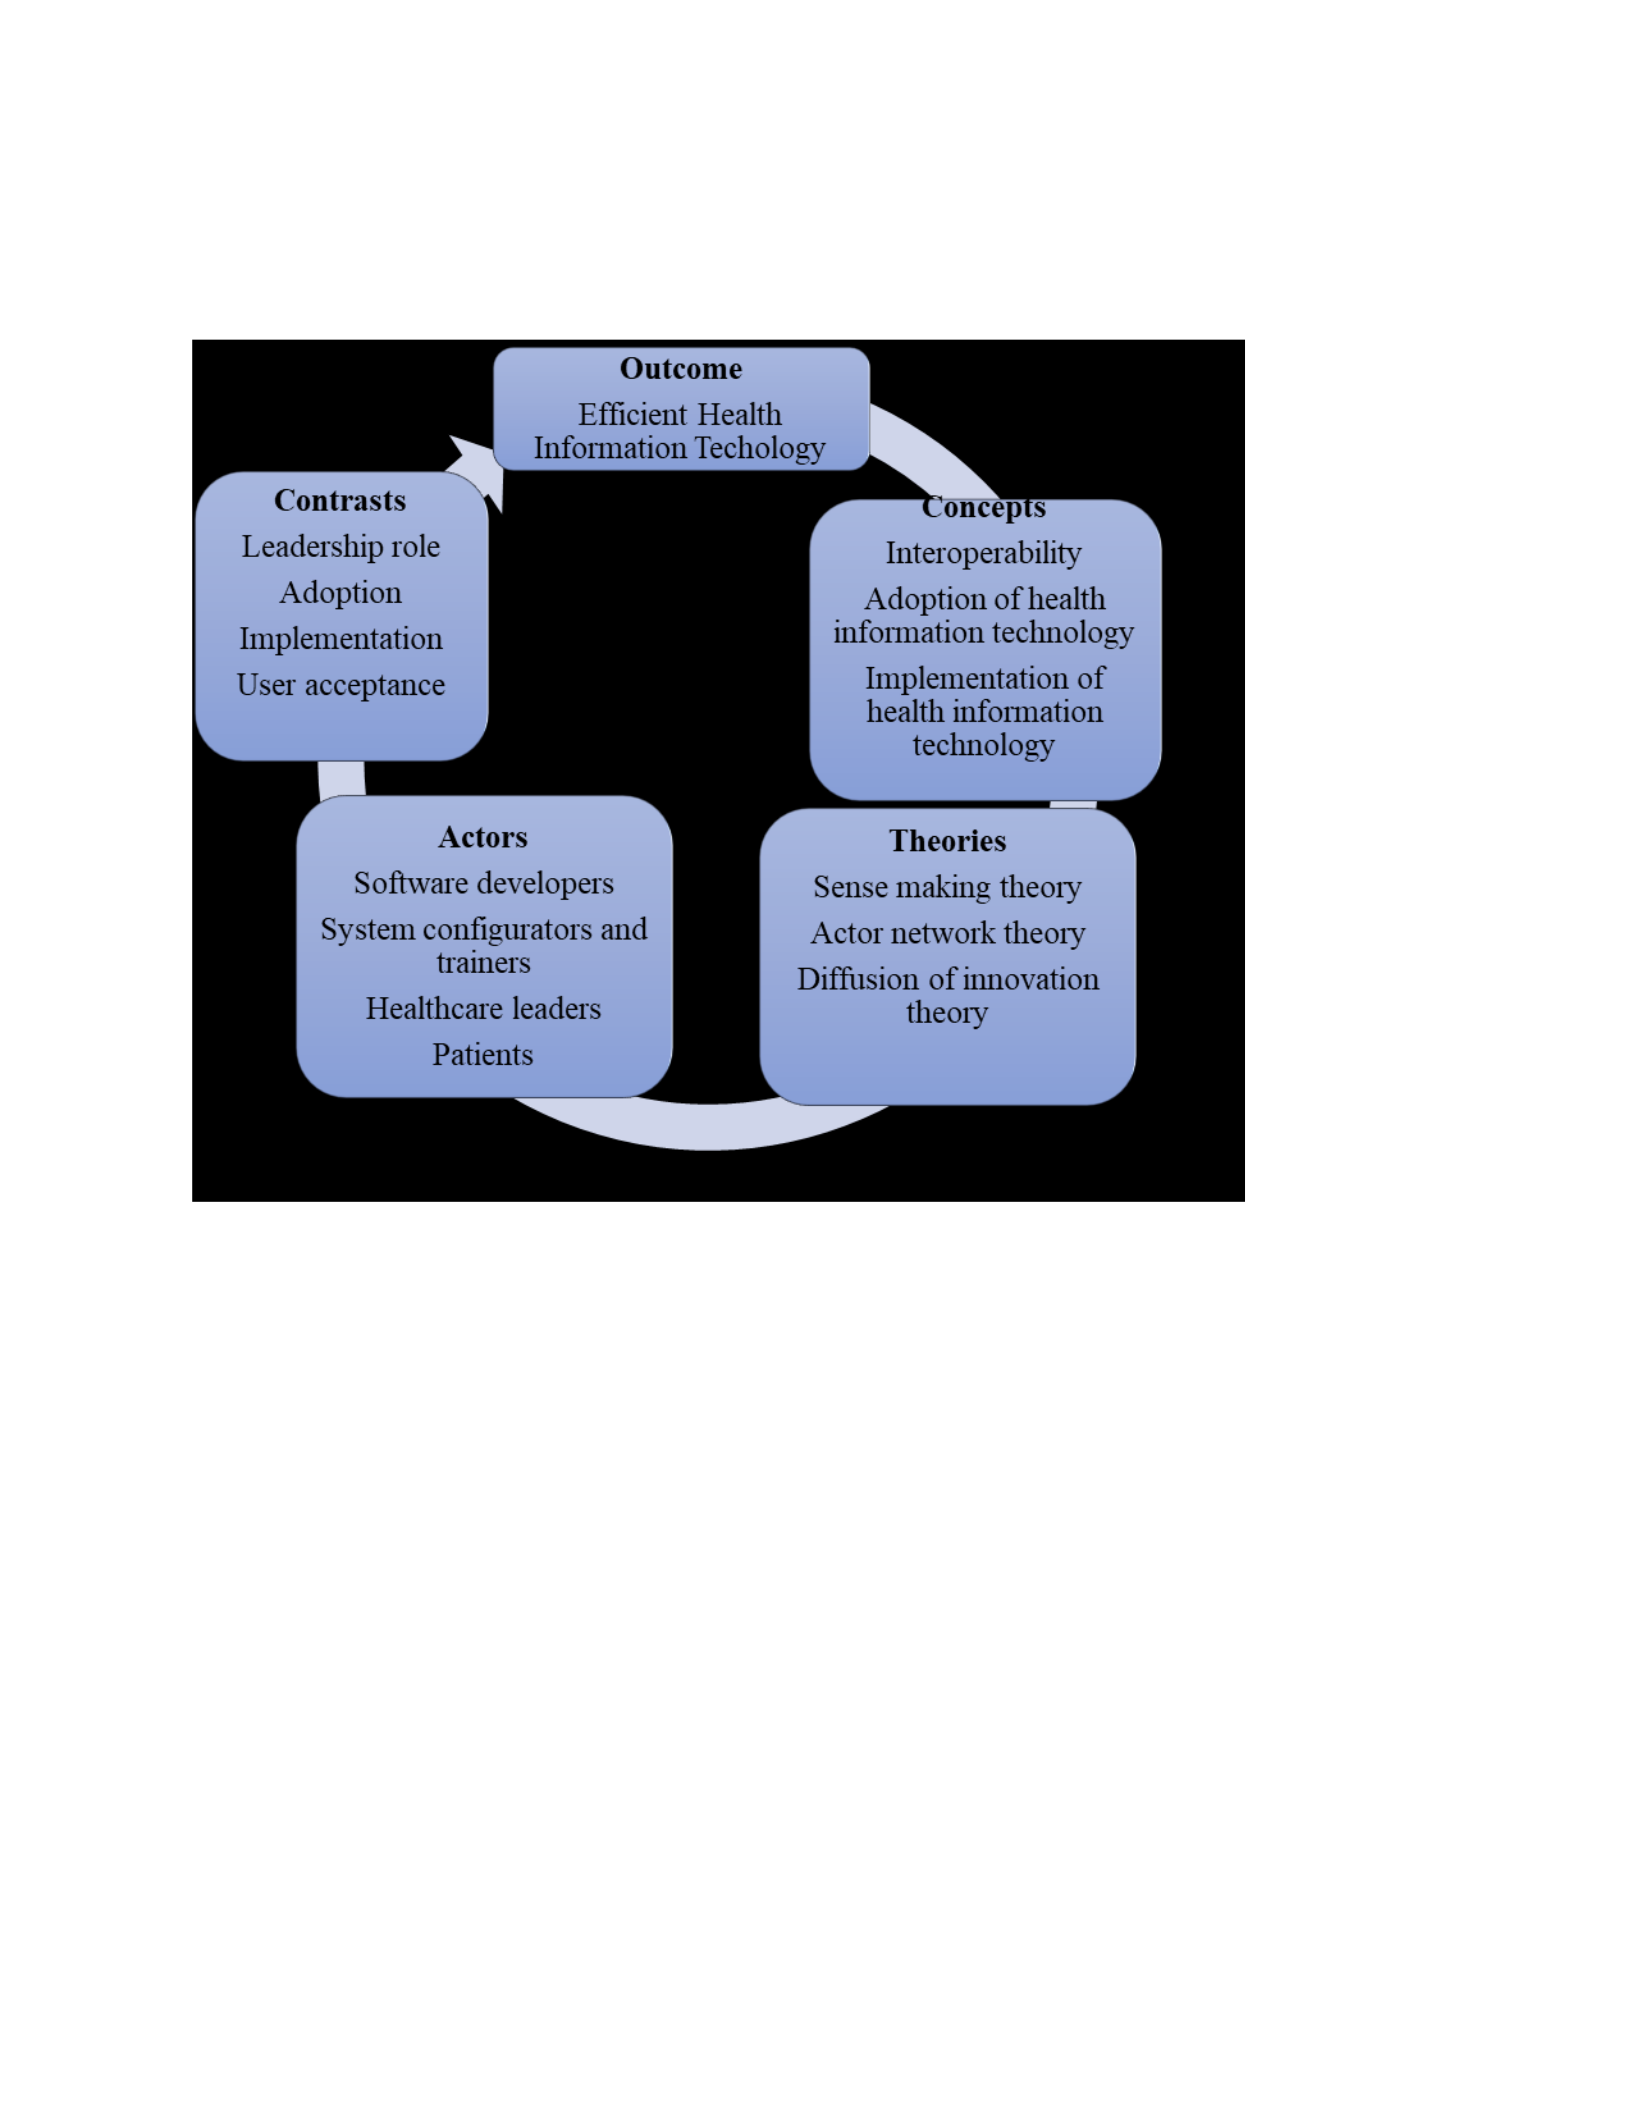
15
Figure 1
Original Conceptual Framework
The diagram above shows that there is a relationship amongst the elements included in
this research framework. Green (2014) stated that the conceptual framework is a structured set of
interrelated elements that specify the nature of the relationship between the variables in research.
It is formulated with the purpose of understanding the problem.
Concepts
Lack of Interoperability Among Health Information Technology Systems
According to Wang et al. (2019), the lack of interoperability among health care
information systems impacts the performance of health information products. Such impact may
cause delays in assessing the correct medical information in a proficient manner leading to

16
serious medical errors which result in unexpected disruptions of health care delivery. Hence, this
relates to the specific problem which states that the mismanagement of health care information
disrupts health care delivery and affects the firm’s business reputation.
Adoption of Health Care Information Technology
Wang et al. (2019) stated that health care compared with other industries have been slow
in adopting technology because of a number of complex reasons interrelated to social and
technical issues within wider organizational environment. These issues may impact the
improvement of quality and safety in health care delivery. This concept relates to the specific
problem since it does demonstrate that there are management issues in the adoption of health
care information technology within health care organizations and highlights reasons for that.
Implementation of Health Information Technology
The concept of implementation affects the efficient management of health care
information technology due to reasons such as user acceptance, motivation to use the system,
confidence, support, integrity and sharing of information to improve patient care and overall
health care delivery (Wang et al., 2019). This concept supports the specific problem by citing
some of the phases that exists and why. Furthermore, the need to address them in order to
provide efficient health care.
The findings agreed with the literature and the concepts of interoperability,
implementation, and useability due to the transition from paper to electronics and challenges
related to functionalities and also the need for interoperability between coordinate systems
impacting implementation, adoption, and useability. While electronic health records are
beneficial in maintaining health care records, its transition from paper to electronic can be very
costly regarding staff training and implementing the software required (Magruder et al., 2018).

17
According to Meinert et al. (2018), due to healthcare organizations' size and complexity, there is
a significant challenge surrounding realistic goals and timelines while managing the eminent
change needed for existing individuals, systems, and processes.
Theories
Sense Making Theory
According to Shachak et al. (2019), the sense making theory deals with constructing
something such as the introduction of new technology within an organization. It focuses on the
relationship between cognition and action mechanism for dealing with unexpected events. For
instance, during the implementation of health information technology, if not managed efficiently,
there may be some interruption which may disrupt the organization’s ways of performing work.
This theory relates to the specific problem in that it does illustrate that if not managed well,
health information technology can result in medical errors leading to the disruption of health care
delivery which will impact the firm’s business reputation.
Actor – Network Theory
Cresswell et al. (2010) stated that actor – network theory studies the relationship that
links people and technology in dynamic networks of position practices. The authors suggest that
it provides ways of viewing technology in shaping organization’s processes, specifically in
dealing with complexities of the introduction of technology in health care systems. This theory
relates to the specific problem because it affirms the complexity that may arise as employees
have a link with technology in carrying out the organization’s processes, more specifically in
health care settings. It can be helpful in investigating the health information technology
implementation process in order to address any management issues which may arise.

18
Diffusion of Innovation Theory (DoL)
According to Ljubicic et al. (2020), diffusion of innovation theory focuses on analyzing
channels for communicating innovation among members of an organization in a given unit and
the characteristics that determine its adoption and value; compatibility and consistency with the
organization’s existing processes; complexity and observability. This theory relates to the
specific problem because it reinforces the importance of understanding key aspects of efficiently
dealing with the adoption of health care information technology as it impacts how health care
professionals manage it in providing quality health care.
The findings indicating that the inefficiencies were due to the complexity of the
healthcare system agree with the Actor-network theory as it studies the relationship that links
people in a dynamic network of position practices. The findings, which revealed that LGH used
robust policies and procedures to ensure the efficient management of health information
technology, corroborated the diffusion of innovation theory, which, according to Ljubicic et al.
(2020), focuses on communicating innovation among members of the organization in each unit
to help determine its adoption, value, compatibility, and consistency with the organization’s
existing processes. The current infrastructure of healthcare is made up of health information
comprising various forms, making it difficult to process (Lehne et al., 2019).
Actors
The actors in this context will be comprised of software developers, system configurators
and training support, clinicians, health care leaders, and patients.
Software Developers
They relate to the specific problem in that they need to ensure that the software to be
applied to health information technology corrects the issues that may be resulting in errors

19
stemming from design, development and implementation that support efficient management
(Sittig et al., 2018).
System Configurators and Trainers
They are related to specific problem solutions because they can alleviate problems arising
from poor system design which can lead to errors in the system development and configuration
(Sittig et al., 2018). They can also train the users since they possess the right skills and
knowledge to solve systems’ problems.
Health Care Leaders
They relate to the specific problem solutions in the sense that hold the key role in
ensuring that the problem stemming from management issues in health care information
technology which may result in the disruption of health care delivery are effectively dealt with.
Clinicians
They are there to learn how to effectively utilize and manage health care information
technology to enable them to provide proper care to the patients. In doing so, the specific
problem can be addressed.
Patients
According to Sittig and Singh (2015), because of recent advances in patient centered care
and the development of personalized health care record as well as other home monitoring
systems, patients and care givers also need training in managing health information technology.
The findings, which revealed that some of the inefficiencies were due to software or
hardware issues that often-caused system slowdown and led to inefficiencies, agree with the
importance of software developers as a component of the actors' element in this study.
Healthcare providers must work with various hospitals with different kinds of healthcare records;

20
they need help learning and remaining proficient with every software. Because of that, they tend
to utilize the ones they are more familiar with (Carayon et al., 2012). The findings corroborated
the need for improved system design and tools by system configurators and trainers. As such
supports the importance of training to learn the system and information across all systems and
the need for continuous technical support from the technology division of the organization. The
findings further agreed with the healthcare leadership component that, if applied, could yield the
efficient management of health information technology. Lack of adequate training and
competence contributes to healthcare professionals' lack of awareness of health information
technology issues (Rahman Jabin et al., 2022). As overwhelmingly expressed by the medical
providers in this study, providing effective learning within the EMR system with a goal of
training in different positions and tailor-making to individual roles to ensure that relevant
information provisions to use HIT efficiently. This clinician's role is important in assessing the
necessary requirements for HIT efficient adoption and useability. Healthcare organizations need
to have user-friendly EHR systems and digital tools as well as strengthen the clinician's e-care
competencies through organizational and regional actions (Vehko et al., 2019).
Constructs
Leadership Role
According to Sinha and Sengupta (2020), as organizations are increasingly utilizing
intensive technology due to current digitalization, one of the most significant influences is the
leadership support regarding cultivating and sustaining training initiatives for regular, systematic,
and training programs in information technology. This role is very important and since it relates
to efficient management of health care information technology, it is essential that organization’s

21
leadership influences, supports and equip their employees with all the up-to-date appropriate
technology and skills sets required to effectively manage health care technology information.
Adoption
Wang et al. (2019) stated that healthcare information technology does not only
encompasses human factors considerations, but also other issues such as strategies employed in
introducing the technology and the way they are adopted by various stakeholders within the
organization. This variable relates to the specific problem because it affirms that employing
strategies for efficient adoption of health information technology is the key to an effective
management of health care information technology.
Implementation
Balancing strategic implementation decisions in health information technology is critical
because it ensures that the unprojected outcomes resulting from inefficient implementation do
not result in patient harm (Sinha & Sengupta, 2020). This relates to the fact that it is critical to
implement health information technology strategically, so it does not affect patient safety
resulting in medical errors which negatively impact the firm’s business reputation.
User Acceptance
Ketikidis et al. (2012) stated that it is important to understand the user’s acceptance in
health information technology since it impacts successful implementation and the
accomplishment of organizational goals with regards to patient data. This acceptance factor is
very critical in the sense that it supports and explains the ineffective management of health
information technology caused by low or lack of user acceptance that can impact negatively on
the accomplishment of the organization’s goals of efficiently delivery health care resulting in the
negative business reputation.

22
The findings indicating that healthcare leaders use robust policies and procedures which
they continuously update as required, agreed with the contrasts component of senior leadership
in healthcare that it holds a significant role in ensuring the efficient management of HIT, and that
leadership is an essential factor in the management and success of the organization's projects
because it drives people, partnerships, resources, processes, strategy, and planning (Saranto et
al., 2019). The findings corroborated that contrasts such as adoption, implementation, and
acceptance were highly caused by inadequate training in HIT systems like EHR, leading to
clinicians' inability to communicate and coordinate efficient quality care delivery. Inadequate
training on EHR impacted the clinicians' ability to communicate and coordinate efficient care,
and lack of trust was attributed to some inaccuracies in the data entered, unclear notations, and
delayed data entry (Rathert et al., 2019).
Relationship Between Concepts, Theories, Actors, and Constructs
The concepts and their agreement with findings affirmed that there is a problem with the
management of health information technology due to interoperability, adoption of health
information technology and implementation of health information technology. If these aspects
are not well managed can result in medical errors leading to the disruption of health care delivery
which can impact the firm’s business reputation. The theories, namely: sense making theory,
actor-network theory, and diffusion of innovation theory describe how if new technology is not
well managed can disrupt the organization’s way of performing its work. Additionally, the
theories recognize the complexities which occur with the introduction of new technology in the
health care system and suggest that if not well managed can impact how clinicians manage it in
providing quality care.

23
The actors are namely software developers, system configurators and trainers, health care
leaders, clinicians, and patients. To manage health care information technology issues efficiently,
it is necessary to have the above-mentioned actors. For instance, the software developers correct
problems which may stem from errors in the design, development, and implementation. The
system configurators and trainers address the issues resulting from poor configurations and
training. Other actors like the health care leaders ensure that the management issues stemming
from health information technology are dealt with effectively. Clinicians and patients must be
provided with the necessary training to enable them to utilize and manage health care
information technology to provide proper care. Lastly, the constructs namely leadership role,
adoption, implementation, and user acceptance also play a major role as it relates to the problem
statement like the rest of the elements discussed above. For instance, leadership roles are
important in influencing, adopting, supporting, and equipping employees with the appropriate
information required to effectively manage health care information technology, thereby resulting
in efficient management of health information technology and health care delivery.
Summary of the Research Framework
The elements discussed guided by literature review and illustrated using a diagram in this
research framework clearly hold a strong relationship regarding issues surrounding the problem
statement on the mismanagement of health information technology. They provided a basis and
approach of why the problem happens and how it happens as well as what steps to pursue to
address it.
Definition of Terms
Electronic health records (EHR): Electronic systems that collect and present patient’s
data during the delivery of care (Kim et al., 2019).

24
Electronic medical records (EMR): The electronic storage system that store large
amounts of the patient’s administrative data which is made up of demographic and clinical
information (Souri et al., 2017).
Electronic health (eHealth): Refers to health services and information delivered or
enhanced through the Internet and related technologies (Varsi et al., 2019).
Health information technology (HIT): involves the exchange of health information via an
electronic environment (Health Information, 2019).
Interoperability: From a clinical perspective, refers to the ability of systems to exchange
electronic health information without any major effort by the user (Adams et al., 2017).
Mhealth: The medical and public health delivery that involves the use of electronic
devices such as mobile phones, patient monitoring systems and other personal digital assistants
(Chow et al., 2016)
Telemedicine: The delivery of health care at various distance location through the use of
electronic health system and other telecommunication devices (Serper et al., 2020).
Assumptions, Limitations, Delimitations
This paper section discusses this study's assumptions, limitations, and delimitations.
Assumptions are perceived as true research in a given organization's sample population,
questionnaire, and the like (Theofanidis & Fountouki, 2018). Limitations are potential areas for
improvement in a given study that is usually out of the researcher's control and can impact the
study's results (Theofanidis & Fountouki, 2018). According to Theofandis and Fountouki (2018),
delimitations are considered limitations consciously set by the researchers because of the
boundaries or limits of their study.

25
Assumptions
The researcher used three assumptions in this study. The first one was derived from the
literature review pertaining to the subject matter which makes it worth discussing. Sittig et al.
(2020) agreed that health information technology offers great benefits. However, if not managed
efficiently, it can present a multitude of challenges which must be addressed in order to continue
to gain its effectiveness, reliability, and efficiency. The second assumption was that clinician
participants in the study will provide truthful information. The third one based on a qualitative
case study assumed that solid information pertaining to the subject matter will be discovered.
Literature review poses potential risk associated with quality and trustworthiness
(Snyder, 2019). To mitigate that, Snyder (2019) suggested evaluating the quality of the literature
to ascertain its rigor for quality research. Other methods the researcher used included assessing
whether the literature is obtained from scholarly and peer reviewed journals (Theofanidis &
Fountouki, 2018). Questionnaires pose potential risk associated with ethical issues (Creswell &
Poth, 2018). The ethical issues which may arise in the researcher’s specific topic and research
design relate to informed consent which adheres to the respect of the participants right to avoid
the feeling of coerced into the participation with regards to divulging information to the
researcher, as well as the time and place of the meeting; further, confidentiality assurance to the
participants is critical to make sure that the privacy of the individuals will be protected. In
addressing these ethical issues, before any data collection is done, an approval must be obtained,
a consent form be given to and signed by the participants (Creswell & Poth, 2018). A
confidentiality statement shall be designed and signed by the participants and their privacy will
be protected by using pseudonyms for each individual. The data collected will be validated for
reliability before it can be interpreted (Creswell & Poth, 2018). In this study, the researcher

26
sought approval from the Lancaster General Hospital IRB. Upon approval, the researchers sent
consent letters to the participants to sign and return before resuming the interviews. To protect
the privacy of the participants, the researcher granted them anonymity. Case studies pose the risk
of recall bias since case study research is nonrandomized and does not represent a large
population (Ridder, 2017). According to Yin (2018), using a well-informed theoretical
framework to guide a qualitative case study can improve consistency, rigor, and trust.
Limitations
According to Ross and Bibler Zaidi (2019), limitations are weaknesses identified in a
research design that may impact the results and conclusion of the study. First, drawing on themes
from the literature review has potential limitations because it covers various health information
technology topics. At the same time, the researcher’s study was only concerned with
management issues with health information technology. To mitigate this, themes applied to the
study were based on the applicable ones. Second, limitations arose from interviews administered
to a specific sample of clinician participants based on their knowledge and experiences with
health information technology. To mitigate this, the researcher expanded the participants to
include a wider sample of healthcare workers, comprised of quality managers, health information
managers, informatics specialists, and the like, to provide a counterbalance.
Delimitations
The scope of this study was delimited to administering interviews to specific healthcare
workers with the knowledge, skills, and capabilities of using health information technology since
they have witnessed its successful adoption and implementation. These participants included a
team of professionals at the Lancaster General Hospital, specifically Medical Doctors, Doctor of
Nursing practitioners, nursing practitioners, clinical informatics in nursing administration,

27
managers of health informatics, and informatics specialists from various divisions within the
LGH. The study was limited to Lancaster General Hospital in Lancaster, PA. About four years
ago, Lancaster General Hospital received the highest recertification from Health Information and
Management Systems Society (HIMSS) on the Electronic Medical Records Adoption Model
(EMRAM) for inpatient and ambulatory services (Lancaster General Health.org). The study used
generic interview questions created by the researcher based on the research questions. Even
though the study was conducted at Lancaster General Hospital, the findings could be generalized
to other healthcare organizations within the United States.
Significance of the Study
Health information technology utilization in the healthcare industry has been found to
improve the quality of healthcare delivery, prevention of medical errors, decrease paperwork,
increase administrative efficiencies, and expansion of access to affordable health care (Health
Information, 2019). Yoo et al. (2016) stated that the adoption of different types of health
information technology can lead to potential benefits of improving healthcare quality, healthcare
workers efficiency, satisfaction, and safety to patients as well as healthcare providers. However,
health information technology at different levels of adoption and integration can pose some
challenges regarding the following: structure of healthcare organizations; tasks; people
incentives and information decision process.
The efficient management of health information technology results in the provision of
real time patient information needed to deliver quality care. If not delivered in time, it can result
in undesirable outcomes such as delayed treatment, uninformed decisions, inefficient resource
use and medical errors, thereby impacting the health care organization’s business reputation. The
essence of this study was to explore and analyze issues pertaining to the management of health

28
information technology. This study will be useful in understanding issues surrounding the
management issues of the subject matter. The contribution of this study would be of interest to
scholars in healthcare management, healthcare providers and healthcare organizations. The
findings in it will add more knowledge in the subject matter and serve as a base for further
research where other researchers could identify the gaps.
Reduction of Gaps in the Literature
The review of the literature on health information technology captures some of the
aspects that confirm that even though its adoption offers numerous benefits, there are issues
surrounding its management. In light of this, it is necessary to study and analyze the root cause
of the issues. According to Sittig et al. (2018), health information technology still requires
substantial improvement in order to offer reliable and efficient use for patient care. Examining
the issues related to health information technology management thoroughly show that safe
effective design, development, and its use requires a shared responsibility and focus on the
people, processes, environment, and the technology involved (Sittig et al., 2018). Palojoki et al.
(2017) agreed that health information technology such as electronic health records offer benefits
that include improved health care, reduced clinicians’ workloads, cost effectiveness and error
reduction. However, state that the use of this type of technology can also pose new risk related to
safety since they tend to disrupt the traditional norms of the clinicians. Because of that, there is a
need for more information regarding the efficient use of electronic health records to prevent the
risks (Palojoki et al., 2017). Some of the techniques suggested by Palojoki et al. (2017), include
developing methods of supporting user awareness as well as monitoring and managing.
Although the research applied using the literature review revealed numerous pieces of
information pertaining to the subject matter as well as other aspects of health information

29
technology; there is still much that remains open for study. The gaps include the following:
According to Singh and Sittig (2016), the adoption of health information technology has resulted
in the reduction of errors. Comprehensive data information technology related to safety event
capturing these errors has not been established. While electronic health records have been widely
adopted in the health care industry, there is still a major part of the segment facing barriers to its
adoption (Kruse et al., 2016). Because of that, there is a need to research why the barriers exist.
The newest wearable health information technology facilitates early detection and treatment of
patient’s illness.
As they become more widely used, they pose some risks (Kowalski et al., 2017). Hence,
the need to find out what proactive assessment methods healthcare organizations can utilize to
mitigate the associated risks (Kolwaski et al., 2017). Since this study sought to examine the
factors pertaining to the inefficient management of health information technology, the causes and
impact on the health care organizations in the provision of quality care, as well as what the
leadership in health care have done to address them, it will add to the literature gaps that promote
efficient management of health information technology. Additionally, the review of the literature
shows that the subject matter has been discussed, but only a few scholars have specifically
discussed the management issues surrounding health information technology as it impacts an
organizations business reputation. The researcher believes that this research will rekindle the
interest which will encourage health care managers to embrace it because it is beneficial for best
business practices.
Implication for Biblical Integration
The biblical perspective demonstrates and reinforces the significance of business research
as a means of advancing God’s purpose for business on earth. This section of the paper will

30
discuss the process of conducting business research from a biblical perspective and how this
study will fulfill this requirement.
Faith is the believe in God based on spirituality. It is confidence in the truth which one
believes, hopes, and embraces. Business research is a calling from God. This secular notion of
faith capital embodies an energizing attitude that drives a group toward its goal and nurtures the
realization of reform goals and transformative organizational learning. In conducting the research
as a Christian, one is influenced by Christian values and beliefs to follow more of the research
approach that has some features which embody the Christian worldview that deals with the
natural world and endorses culture and beliefs. God has revealed Himself through nature and
designed mankind with an innate curiosity for discovering this truth (John 1:9). Since all truth
ultimately comes from the mind and hand of God, studying natural events, when conducted from
a Christian world and life view, eventually will point the researcher to the Designer of the truth
being studied (Psalm 19 and Romans 1: 17-32). And that ye study to be quiet, and to do your
own business, and to work with your own hands, as we commanded you (1 Thessalonians 4:11).
As Christians we follow a similar method in that we often ask questions about life and destiny.
We research and draw conclusions based on the research findings; as well as testing our
experiences against our conclusions (Busenitz & Lichtenstein, 2019).
This study dealt with management issues surrounding health care information technology
which is one of God’s creations. It represents what Keller (2014) described as work like
cultivation. Genesis 1:28 “Humans are commanded to till and subdue the earth.” We as
cultivators, we change the land and make it fruitful; meaning that we are care called upon to
engage in continuous improvement which adds value to our productive processes, outputs, and
whatever work we are engaged in. This is the cultivation process that adds value. From the

31
business research perspective, this means that as a researcher, one engages in various processes
of carrying out the research for a solution to a problem or an intended project to change it to a
meaningful status. Conducting research to address management issues in health care information
technology enables one to creatively find ways of improving business and contribute efficiency
as well as increase revenue in efforts towards the advancement of God’s purpose for business on
earth. Beavers et al. (2020) stated that since God tells us to create and develop our world, there is
value in within objects which include all forms of technology, which if not handled appropriately
during interaction with other entities may lead to negative impact such as mistreatment of other
people. This mistreatment is regarded as being unethical to our loving God.
Benefit to Business Practice and Relationship to Cognate
According to Ford et al. (2010), U.S. hospitals are implementing technologies to meet
business needs. There are numerous benefits associated with the utilization of health information
technology. They include the following: (a) improvement of quality care delivery through
prevention of errors, and (b) reduction of paperwork resulting in increased efficiencies and
expansion of affordable health care (Health Information, 2019). Gauthier et al. (2018) stated that
health information technology enhances the performance of health care teams with increased
efficiency in data collection and information exchange. Thus, leading to cost savings. Other
components of health information technology such as telemedicine has promoted the facilitation
of care delivery where the provider and patient are in separate distance locations resulting in cost
effectiveness (Shi & Singh, 2019). According to Kruse et al. (2018), health information
technology has drastically transformed how the health care industry operates. With the adoption
of one of its major components known as electronic health records (EHR), there has been a
creation of overall public health awareness. This has contributed to the expansion of care

32
delivery into geographic areas where barriers to access previously existed. The use of electronic
health records has resulted in the reduction in patient length of stay and the possibility of
readmission in a health care facility as well as providers increased productivity. Thus, providing
potential cost savings and overall efficient health care management and delivery systems (Wani
& Malhotra, 2018).
Saleem et al. (2016) stated that health information technology has provided valuable data
and helped researchers advance their clinical knowledge. Adopting digital technologies in health
care has also enabled use of cost-effective medical devices to transmit information to the health
care provider (Saleem et al., 2016). Other benefits to business practice as highlighted by Khalifa
(2017) included the following: Improved information access, increased productivity, improved
efficiency, accuracy in billing and coding as well as reduction in expenses related to paper
recording. According to Mitchell and Kan (2019), World Health Organization (WHO) classified
health information technology benefit to functions into the following categories: First, better and
more efficient provision of patient’s health information. Second, the support of the health care
employees and managers in patient diagnosis and treatment. Third, provisions of verifiable
demographic and clinical records. Fourth, the capability to provide health care managers with
operational and strategic information about drug availability, finances, and the management of
employees.
Overall, the efficient use of health information technology can result in benefits such as
improved quality care due to rapid access to patient information, improved productivity, and
financial improvements related to more efficient billing and the like (Khalifa, 2017).
Additionally, with components of electronic health records with patient portals, it can facilitate
timely health information exchange (Health Information, 2019). However, if not managed

33
efficiently, health information technology can result in some undesirable outcomes, therefore, to
realize its efficient use, it is imperative that the challenges associated with it be addressed (Sittig
et al., 2018). This study is related to health care management because it sought to understand and
address the problems surrounding the management of health information technology as it
impacts health care delivery business.
Summary of the Significance of the Study
The results of this study will contribute to the efficient management of health information
technology for the intended industry of health care. It will form a basis of research on other
aspects of the subject matter. Through the reduction of gaps in literature, there are more newer
factors that still need to be researched in order to solidify management issues surrounding health
information technology. In light of the numerous benefits it offers to business practices, it is
clear that using it efficiently will continue to accelerate the successful delivery of health care and
result in other positive outcomes such as cost effectiveness, productivity, revenue growth and
profitability. Integrating the biblical perspective in the study of the subject matter reinforces
God’s calling to cultivate work as a means of delving into the soil of information through data
collection and analysis as a foundation to a solution of a problem. Thus, advancing God’s
purpose for business on earth.
A Review of the Professional and Academic Literature
The efficient use of health information technology by health care providers and
professionals can bring centered health information and services (Healthy People, 2020).
Because of that, the following potential benefits can be realized: improved health quality and
safety, improvement in health information infrastructure, facilitation of clinical decision making,
and the like (Healthy People, 2020). If health information technology is not used efficiently, it

34
can result in undesirable outcomes (Sittig et al., 2020). The purpose of this literature review is to
explore and understand the use and management of health information technology from its
benefits and challenges perspective through the review of professional and academic literature
thereby gaining a clear understanding of the problems it poses related to the disruption of quality
care delivery, resulting in a negative impact on the organization’s business reputation and gain a
clear understanding of the benefits associated with its efficient use. This section presents a
review of the literature on health information technology within the context of issues
surrounding its management.
The purpose of this review is to systematically gather comprehensive information on the
subject matter and analyze, synthesize as well as summarize the findings. To do so, the literature
review outline will discuss the anticipated themes related to the subject matter under the
following headings: (a) quality and safety, (b) electronic health records technology, (c) health
information technology and efficiency in care delivery, (d) innovative health information
technology, and (e) challenges with the use of technology in health care. The review will discuss
the discovered themes under the following headings: (a) coordination of health care with health
information technology; (b) health information technology, privacy, and risk; and (c) physician
burnout related to health information technology. The references used in this literature review are
scholarly peer-reviewed journal articles of which 75% were published within the last five years.
In addition to this, additional information was obtained from other references including books
and credible government websites.
Quality and Patient Safety
According to Magrabi et al. (2016), while health information technology offers a wide
array of benefits in clinical medicine such as reducing clinicians’ workload, cost, and errors as

35
well as the improvement of health coordination; if not implemented and managed efficiently, it
can result in new errors that can affect the safety and quality of care. Kim et al. (2017) concurred
that the increase in the adoption of health information technology has resulted in numerous
benefits. However, problems with information technology can lead to the disruption of health
care delivery and most likely the increase of unforeseen errors that can also impact the safety and
quality of health care delivery. Thus, lead to patient harm. To continue to gain the benefit and
manage the new issues there is a need to understand the ways in which information technology
can disrupt care delivery and affect patient safety. According to Kim et al. (2017), this can be
done by classifying the problem into five main categories as follows: interactions, information
received, decision changed, case process altered and outcome change. With respect to
interaction, the contributing factors include training, cognitive, interruption, integration,
workflow, and the like. Factors related to the other four categories include issues such as wrong,
missing, or delayed information. Sittig et al. (2018) stated that health information technology has
some great potential to improve health care delivery, however, it can also pose some challenges
which involve ensuring safety in its use in clinical settings. According to Sittig et al. (2018)
examining the issues thoroughly shows that safe effective design, development, implementation,
and its use requires shared responsibility and focus on people, processes, environment, and the
technology involved. Health information technology requires substantial improvement in order
to offer reliable and efficient care to the patient (Sittig et al., 2018).
Feldman et al. (2018) stated health information technology is used in healthcare settings
for the provision of quality and patient safety in identifying reportable events before they become
problematic. To fully explore the use of health information technology, it is critical to understand
where to focus health information technology fiscal, human resources, and the expectation in its

36
use in quality and patient safety (Feldman et al., 2018). One concept Feldman et al. (2018)
suggested is that understanding what implementations are being applied by other organizations
relative to quality human resources planning, cost management and outcomes. Furthermore,
strong organizational leadership can successfully direct implementation and impact culture as
well as structure health information technology with developers.
Alotaibi and Federico (2017) described health information technology as the application
of information utilizing computer hardware and software that works with storage and retrieval of
information. The sharing and use of health information for knowledge, communication and
decision making. According to Alotaibi and Federico (2017), health information technology is
comprised of various forms of technology which can be described as simple to more advanced
decision support systems. These forms of technology offer numerous benefits which include the
improvement and transformation of health, resulting in the reduction of errors, improving
medical outcomes, care facilitation, improvement of practice efficiency and the like (Alotaibi &
Federico, 2017). Alotaibi and Federico (2017) stated that to some extent, health information
technology can impact patient safety. To ensure that health information technology results in
desirable outcomes, health care organizations need to be selective in the technologies they invest
in. In the study they conducted to investigate the effect of health information technology safety
on patients, Alotaibi and Federico (2017) found out the following: First, using computerized
order entry can improve patient safety because they support additional services such as electronic
test ordering and consultation. As such, this form of technology improves the safety associated
with the manual handover from one care giver to another and reduces medical errors which may
arise in the handover process. Second, automated dispensing cabinets ensure controlled
dispensing and track medication allocation which reduces medication errors. Other health

37
technologies such as electronic portals improve patient health outcomes through the provision of
disease awareness and self-management (Alotaibi & Federico, 2017). Adams et al. (2017)
defined interoperability from a clinical perspective as the ability of a system to exchange
electronic health information from other systems without any special effort by the user.
Electronic health technology is a various level of interoperability with other health information
technology within the same healthcare organization or the external one (Adams et al., 2017).
According to Adams et al. (2017), several stakeholders have advocated for the necessity of
electronic health records interoperability because of improved healthcare delivery and most
critically, efficiency. Without good interoperability, patient safety can be affected. In a study
they conducted using patient safety event reports, Adams et al. (2017) found out that the majority
of interoperability challenges in clinical settings stemmed from electronic health records
receiving information from other health information technology; but not from electronic health
records sending information to other systems. Most of the electronic health records happened
within the provider organization not impacting the patient’s safety.
Electronic Health Records Technology
To understand the evolution in the electronic health record, it is important to know the
history of health care record keeping. Initially, EHRs were developed and used in a number of
academic inpatient and outpatient medical facilities. None contained all the information in the
paper chart and most EHRs today are still a hybrid collection of computerized and paper data
(Evans, 2016). The evolution of EHR was a necessary step for continuity of patient care. Patients
have had difficulty getting information from different providers, because usually there was no
unified system for providers to use as a reference for previous care received by patients. In the
late 1980s and early 1990s, hardware technology became more affordable, powerful, and

38
compact; in addition, with the emergence of web based EHRs, the use of personal computers,
local area networks, and the Internet provided faster and easier access to medical information
(Evans, 2016). As technology has evolved, there have also been concerns about the care of
medical records. As EHR use is becoming increasingly more global, there has been a move
toward international health information system implementation.
According to Evans (2016), the following includes some of the newer functionalities of
EHR: (a) EHR records are now being created, used, edited, and viewed by multiple independent
entities including primary care physicians, hospitals, insurance companies, and patients; (b) they
are increasingly being used in primary care exam rooms to document and access patients’
records along with online medical information and decision-making tools and prescribe
medications; (c) EHR’s have transformed the patient-clinician interaction through clinician-
patient email, virtual consults, and telemedicine; (d) now with health information technology that
facilitates the management of data and images, results from external laboratories can now be
integrated into electronic health records; (e) providers now have the capability of using order
sets, voice recognition, barcodes, and documentation templates to directly enter information into
the EHR and decision support rules along with computerized provider order entry are used on a
daily basis; and (f) mobile health devices can also now be used to capture images from a
patient’s bedside and insert them into electronic health records.
According to Fong et al. (2017), numerous hospitals in the United States have adopted
electronic health records technology to support functions such as clinical information,
computerized order entry, results management, and decision support. However, while these
components of health information technology have resulted in positive outcomes on clinical care
processes, they can pose serious safety issues if not designed, developed, implemented, and used

39
effectively (Fong et al., 2017). In order for organizations to continue to reap the benefits
resulting from the utilization of health information technology, it is imperative that they develop
a detailed understanding of system-induces errors in the healthcare process (Fong et al., 2017).
According to Fong et al. (2017), such a system would produce patient safety event reports which
provide descriptions of safety hazards and errors captured. To improve the analysis of these
reports can be achieved by applying the active learning approach with sample confirmation over
superior vector machine with no active learning. This helps in focusing the value of what is
known as human annotators (Fong et al., 2017).
Ratwani et al. (2016) agreed that electronic health records have the potential to improve
efficiency, safety, and quality healthcare. Ratwani et al. (2016) also believed that it is critical that
they are designed, developed, implemented, and used properly. Among the above factors
mentioned, Ratwani et al. (2016) suggested that useability is one of the major factors impacting
the realization of the full potential. If not well mastered, it can result in inefficiencies and
clinician frustration which can lead to patient harm and safety issues. Useability in information
technology involves developing a deeper understanding of how the clinicians perform their work
in order to have system developed support and cognitive needs (Ratwani et al., 2016). According
to Mamlin and Tierney (2016), the enactment of the Affordable care and the health information
technology for economic and clinical health have led to the expansion and adoption of health
information technology. As a result, almost every U.S. physician has personal experience with
EHR systems. Even though most providers are now using EHRs, the majority are either
unsatisfied or frustrated with their use. There are a couple of ways health care organizations are
supplied with EHRs. The supply for hospitals is from a small number of large vendors and
outpatient practices are from a larger number of smaller vendors (Mamlin & Tierney, 2016). As

40
described by Mamlin and Tierney (2016), each EHR has a unique user interface and approach for
representing and storing clinical information with little sharing of data between them. Standards
to enhance data sharing are appearing, with minor information sharing between health systems,
outpatient practices and other venues.
According to Mamlin and Tierney (2016), the Health Information Technology for
Economic and Clinical Health, requires EHRs to meet meaningful use criteria, documentation
that can improve quality, reduction of disparities, patient engagement, improvement of care
coordination and maintenance of data privacy and security. Mamlin and Tierney (2016) stated
that in recent years, accomplishing a meaningful use criterion has dominated vendor
development and overshadowed the innovative responses needed by medical providers. Mamlin
and Tierney (2016) asserted that EHRs do not improve healthcare quality, efficiency, safety, or
outcomes of care as expected. They remain unsuitable electronic versions of paper charts as their
use focuses more on administrative needs than on patient care, which leads to an increase in the
amount of documentation while decreasing its medical usefulness.
Benefits associated with improving practices and standards for user interactions include
the enhancement of providers' EHR experiences (Mamlin & Tierney, 2016). With the increase in
healthcare applications and other sharable programming platforms, features applicable across
electronic health records also increase, leading to the improvement of clinicians’ options and
experiences. The improvement in the adopted standards promotes the use and sharing of data
(Mamlin & Tierney, 2016). For instance, clinicians accessing a patient’s EHR can see data from
their hospital and all other health systems. This according to Mamlin and Tierney (2016) could
result in less cumbersome. easy, and accurate documentation and enable providers to spend more
time in care delivery. Additionally, capturing data automatically could eliminate administrative

41
tasks. The meaningful use of health information technologies like electronic health records will
help health care managers in the following: identifying quality gaps, identifying the patient’s
unmet needs, and understanding population health and health care needs (Mamlin & Tierney,
2016). Methods to accomplish this would require resources such as the application of fast health
care interoperability resources, automated recording of data describing and storing information
about other data and reassigning the recording management and billing information to trained
specialist (Mamlin & Tierney, 2016).
According to Wani and Malhotra (2018), the proponents of electronic health records
indicate that it has also helped healthcare providers to work with greater productivity and fewer
errors in the diagnosis and treatment of patients. This has led to increased efficiency in health
care delivery. The reduction in errors and the resulting correct treatment has contributed to a
reduction in patients’ length of stay. Wani and Malhotra (2018) also suggested that hospitals who
systematically capture patient’s information and use it for building medical guidelines for
patients’ treatment, have truly helped in reducing length of stay and the possibility of
readmission. They emphasized that with the reduced length of stay in a healthcare facility, there
is a potential cost savings in the overall healthcare management and delivery system. The use of
electronic health records can help alleviate the shortage of providers; a problem which is
currently facing healthcare organizations pertaining to the facilitation of “bed management and
efficient operation” (p. 13) as well as the reduction in the length of stay of patients (Wani &
Malhotra, 2018).
The use of electronic health records has contributed to one of the electronic deliveries of
quality and timely healthcare. With the storage of patient’s information in a computerized
system, it has allowed clinicians to have easy access to the records thereby enabled them to

42
research and manage various diseases information; and making it convenient to check patient’s
information which are readily available and easily accessible (Shi & Singh, 2019). This offers
timely access to the laboratory and imaging results as soon as they become available. With easily
accessible information, it helps the physician to accelerate the diagnosis process as well as the
necessary treatment decision making; thus, giving the patients timely and cost-effective
healthcare services. Additionally, with the EHR, Clinicians are able to monitor patients care and
progress (Chao et al., 2013). Not only has the use of electronic medical records by the physicians
resulted in timely access to the patient’s records, but it has also helped in alerting them of
potential error and making lab values ready when needed (Shi & Singh, 2019).
Health Information Technology and Efficiency in Care Delivery
Hossain et al. (2018) stated that health care technologies facilitate the use of resource-
constrained devices to promote the quality of care. These cost-effective health monitoring
devices have replaced expensive diagnostic tests. The stakeholders have identified the potential
of information technology to reduce health care costs and improve patients’ welfare. Health data
systems improve health care by providing an innovative solution for the diagnosis and treatment
of diseases. Advances in this area have led to the development of wireless networking
technologies such as 5G wireless networks. For instance, 5G-Smart Diabetes technology is used
for the diagnosis and treatment of diabetes (Hossain et al., 2018). The equipment allows the
continuous monitoring of metabolic states of diabetic patients for the provision of appropriate
treatment. It has replaced time-consuming blood sugar tests, which allows making an expedited
diagnosis.
The 5G wireless network enables the delivery of personalized, sustainable, and
comfortable care to patients. The communication network allows data sharing to understand the

43
model of the disease. Digital healthcare technologies facilitate the timely diagnosis of terminal
illnesses such as cancer. Huang et al. (2017) argued that advances in healthcare imaging
technologies have led to an increase in the early detection of childhood cancers. Through timely
diagnosis, continuous monitoring, and appropriate treatment of diseases, information technology
has helped improve the outcomes of the health care system. Health information-based
technology allows physicians to provide more exceptional patient care (Huang et al., 2017).
Electronic medical records inform doctors of possible disease diagnoses and other examinations.
The documents also automatically alert them of potential issues such as drug allergies. The
access to electronic medical records can occur across multiple medical facilities. Therefore, the
information can help physicians handle new patients, especially if they are unconscious or unable
to provide a medical history themselves.
Digital health records capture patients’ information and help in making an appropriate
treatment plan. Likewise, technology improves the coordination of care and information among
laboratories, healthcare professionals, and other health-related organizations. The physician
sends patient data with the required tests to the laboratory. The personnel then capture the tests
results in the computerized system for the physician to view (Huang et al., 2017). After diagnosis
and the establishment of the treatment plan, the information is sent to the pharmacy to dispense
drugs. The treatment plan is stored in the system and can be reviewed in the future by any
physician. With a comprehensive patient history stored in the system, it enables physicians to
access and treat diseases and prevent the wrong prescription of drugs. These data can be
exchanged via the computerized system among different teams to enable careful coordination of
care (Huang et al., 2017).

44
The provision of quality care requires a holistic approach and digital platforms that can
allow healthcare professionals to provide exceptional care to their patients by sharing important
information with team members. Advances in health care data systems have promoted data
safety by facilitating secure transmission and storage of patients’ information. The technology
introduces an authentication mechanism that protects the transfer of data. Hossain et al. (2018)
asserted that the encryption and decryption features available in electronic systems provide a
unique identifier to promote data security. The verification mechanism in the information system
ensures that an individual can only view their health data, while physicians have access only to
the data of their patients.
Verification systems protect patients’ privacy by preventing unauthorized access to their
data. The innovation of the medical image forgery detection system prevents the wrong
diagnosis, which may lead to a social embarrassment. Cloud computing technology has allowed
health centers to store large data sets at a low cost (Hossain et al., 2018). It relies on backup and
recovery systems to protect against loss of valuable data. Healthcare centers benefit today from
secure data transmission features and safe storage systems as they ask for verification before
accessing the servers. This limits the personnel who access the data.
Health information technology has provided valuable data and helped researchers to
advance their clinical knowledge. The transition from research to practice takes time (Saleem et
al., 2016). Digital technologies have also allowed physicians to implement research findings in
the healthcare settings before the results become obsolete. Appropriate utilization of this data in
clinical decision-making helps improve patients’ health outcomes. Digital technologies provide
tremendous opportunities to integrate recent study findings with clinical information systems,
thus reducing diagnosis and medication errors (Saleem et al., 2016). The systems provide

45
healthcare professionals with up-to-date health data to improve the efficiency of care and boost
the quality of care. This system could help bridge the gap between research and practice, as well
as being useful in the management of various health concerns (Saleem et al., 2016).
Technological advancements in the healthcare system have continuously improved the
delivery of these services in the United States. They have helped promote efficiency by reducing
operation costs and errors in patient data. Digital technologies have allowed the utilization of
cost-efficient medical devices that transmit information to physicians. Advances in medical
technology have had a significant impact on the practices of health care professionals, thus
improving the quality of care (Saleem et al., 2016). They have also provided an innovative
solution for timely diagnosis and treatment of diseases, such as diabetes and cancer. Digital
technologies in healthcare have also promoted data safety by facilitating secure transmission and
storage of patient data. According to Saleem et al. (2016), health information technology
provides researchers with valuable information that helps them to advance clinical knowledge
and improve the quality of care provided to patients. Technological developments have promoted
positive health outcomes and made the process of providing health services more effective.
According to Sood and McNeil (2017), when health information technology is adopted,
implemented, and used appropriately it can result in safer and higher quality care than paper-
based systems because of the following reasons: Improved communication and better handovers
through various tools, real-time monitoring of vital signs that can signal deterioration in a
patient, decision support and rapid response to and tracking of adverse events. There are other
numerous benefits health information technology can offer as outlined by Sood and McNeil
(2017). They are as follows: (a) information to monitor clinical conditions and inform decision
making in chronic disease management, (b) improvement of the processes of care based on

46
evidence of effectiveness, (c) ability to conduct real-time documentation in both structured and
unstructured formats to allow viewing of information in real time, (d) patient access to their
health record and clinical interaction functionality, (e) prompt order entry and results reporting,
(f) medicines management and optimization, (g) innovative workflow pathways, (h) automated
clinical alerting aligned with clinical decision support, (i) centralized approach to data sharing
agreements and consent, and (j) ability to analyze large population datasets aimed at improving
population health.
Sood and McNeil (2017) stated that benefits health information technology will be
attributable to the interoperability service that modern health information technology systems
allow. When this service is applied effectively, it will not only improve direct patient care and
outcomes, but will also reduce administrative costs, allow health care organizations address
unintended variation, and effectively utilize data for research and development (Sood & McNeil,
2017). Without healthcare workforce, health information technology cannot improve care since
the workers are the enablers to change and improve how care is delivered and therefore in its
implementation process, the health care workers must be taken into consideration (Sood &
McNeil, 2017). To maximize the investment in health information technologies, stakeholders
need to take a few matters into consideration. First, there should not be some overpromising of
benefits. Second, there is a need to focus on restructuring workflows and process as technology
is continuously evolving and may require complex changes for organizations to continue to gain
the benefits on quality care, safety, and efficiency. Lastly, healthcare organizations must remain
proactive in fully engaging their workforce as important elements of the success for the entire
system to become efficient (Sood & McNeil, 2017).

47
According to Reddy and Sharma (2016), most businesses and companies including the
health care industry are adopting digital technologies for business growth. While the health care
industry has been successful in the adoption of health informatics in the form of electronic health
records, genomic systems, remote diagnostic, wireless technologies, context aware computing
and cellular technologies, there has been difficulties in adopting other digitalization such as big
data analytics. Several reasons are attributed to the slow adoption. They include privacy issues
and apprehension about customer acceptance. With the successful adoption of this type of
digitalization, Reddy and Sharma (2016) highlighted the following future outlook for the health
care industry: (a) the utilization of electronic health records will replace manual records and
eventually create big data for the provision of care for all; (b) genomics systems will facilitate
customer’s ability to have their personal genomics data for better health and preventative care;
(c) health wearables will allow patients to monitor their health on a continuous basis and seek
professional care in a timely manner as well as practice preventative care; (d) with increased
internet connectivity and digitalization, health care delivery will take place in more locations
than in hospitals alone and would afford remote care delivery; (e) the utilization of digitalization
will help in predicting a major epidemic before it arrives; and (f) through the use of health
information technology, the cost of health care cost would likely be reduced.
Khanra et al. (2020) agreed that among other health care functions, big data has had a
major influence in clinical decision support systems, disease management, and health care
management. Furthermore its strategic approach in adoption by health care organization can
result in business benefits (Khanra et al., 2020). Big data analytics can also pose some major
challenges to the health care industry. They include the following: (a) high initial investment
costs, (b) quality of data may be impacted by lack of well-trained personnel and their resistance

48
to routine organizational changes, (c) quality of insights due to poor quality of heterogeneous
biomedical data, and (d) privacy and security issues related to patient data being exposed.
Kamble et al. (2019) also agreed that big data analytics plays a major role in the improvement of
health care organization’s performance, but also adds that there are some critical challenges
which can affect its adoption. They include privacy, data security and data traceability. New big
data technology will need to focus on the mitigation of such obstacles to function efficiently
(Kamble et al., 2019).
Innovative Health Information Technology
According to Anderson et al. (2017), in response to challenges Trinity Redemption Care
Hospital in Wilmington, Delaware faced in the management of chronic health conditions, this
organization developed a health information technology called care link. This technology is an
enhanced care management support system which was designed to enable patients gain better
health outcomes at a reasonable cost (Anderson et al., 2017). This model specifically supported
patient populations who needed services such as joint replacement, congestive heart failure and
spine injuries. Anderson et al. (2017) stated that this health information technology care link
consists of a number of applications which include the operational data storage that received data
from various clinicians in the hospital. Additionally, care link received real time notifications of
discharge, admissions, and abnormal laboratory test results. Other features included a machine
learning technology and artificial intelligence that enabled medical providers to identify patients
at high risk (Anderson et al., 2017). In the end result, the utilization of care link shortened the
length of stay in the hospital among the patients, as well as reduced the readmission rate. Like
other health information technologies, care link also poses challenges such as significant
financial investments and the need for high level of expertise (Anderson et al., 2017). According

49
to Salway et al. (2020), in an effort to coordinate and improve COVID-19 care, New York City
Health + Hospitals employed the use of innovative technologies tools as they transitioned into a
unified enterprise electronic health record across all its medical facilities. This helped in
accelerating the implementation of a number of technological solutions such as smart notes to
improve clinicians’ efficiency and capability to have rapid medical screening exams and vital
signs monitoring. Specialty order sets and dashboards were created in order to standardize
patient workup and provide information on bed allocation, transfer patients from one hospital to
another depending on the capacity (Salway et al., 2020). Other innovative solutions that were
used included tablets which connected patients with their families. Through the rapid expansion
of health information technology, New York City Health + Hospitals were able to have a better
handle on COVID-19 (Salway et al., 2020).
Walker-Czyz (2016) stated that healthcare organizations are faced with extraordinary
challenges to meet the increasing demand for services. These challenges are numerous, and they
require organizational leaders to find solutions that foster both quality and cost-effectiveness.
Accomplishing these solutions would require the innovative adoption of EHRs at the bedside
because it has the potential to provide effective, patient-centered, quality nursing care (Walker-
Czyz, 2016). According to Walker-Czyz (2016), with the adoption of computerized
documentation there is a potential for the enhancement of the quality and safety of care delivery
through placing evidence-based practice (EBP) standards into the nurse's workflow. The use of
EBP standards of care or bundles of care, structured within the EHR, facilitates nurses’ decision
making by providing a checklist of planned delivery of care, thereby resulting in fostering
compliance with practice standards.

50
Rudin at al. (2017) stated the coordination and management of complex patients requires
the use of analytics and health information technology since they can address the challenges
related to increased health care costs and at the same time improve quality care. However, Rudin
et al. (2017) suggested there is lack of evidence on how effective these systems are. Moreover,
there are challenges associated with the coordination of complex patients such as those causing
health care providers to order unnecessary laboratory testing, repeated imaging, and other
unavoidable hospitalizations. Thus, resulting in the incurrence of more costs (Rudin et al., 2017).
According to Rudin et al. (2017), the innovative use of health information technology and
analytics may help address these challenges effectively because of the following reasons:
Analytics use different types of data that can help create better risk categorization approaches
that bring effective interventions on patients.
Health information technology is made up of tools that can be used for prompt
communication and decision making; more especially for complex patients who may require
large care teams as well as generate high volume of data during their care. In order to solidify the
evidence on the innovative use of these systems, Rudin et al. (2017) conducted some research
with the subject matter expects and derived the following findings: Analytics focused on three
major roles. First, to identify complex patients. Second, to identify the subset of complex patients
who could be helped by interventions. Third, to match subgroups of complex patients to specific
interventions.
Regarding health information technology, Rudin et al. (2017) discovered five distinct
functionalities which are currently being used by healthcare organizations. First, dashboards for
supporting ad hoc and quick discussions among clinicians. Second, patient relationship for care
coordinators to manually track interactions with patients and manage tasks. Third, event alerts

51
triggered by emergency department visits, hospitalization and other clinical events are sent to
care teams. Fifth, the referral tracking and care plans to ensure that the tracking requirements of
the patient’s referral and care. Rudin et al. (2017) stated that these technologies present some
challenges concerning their functionalities to coordinate health care. Analytics have issues
pertaining to poor quality data and lack of novel data types. Health information technology
functionalities include the lack of interoperability between coordinating systems and other
technologies. Based on the findings, it can be concluded that analytics and health information
technology with limited capabilities. To further improve their efficiencies, the challenges need to
be addressed (Rudin et al., 2017).
According to Demiris et al. (2019), the use of innovative tools in information technology
has the potential to support caregivers for cancer patients. This is because such information
technologies can provide access to information from various sources and improve
communication between the patients and caregivers. Demiris et al. (2019) stated that the increase
in the use of mobile applications, communications and other wearable devices have made it
possible for health care organizations to land more and newer opportunities to support
healthcare. More, especially in areas where there are geographic distances and barriers impeding
efficient access to healthcare. These innovative tools have increased the healthcare support for
rural care givers who are often faced with transportation, healthcare workforce shortages and
other specialized supportive services (Demiris et al., 2019). Demiris et al. (2019) stated that as
these types of technology are increasingly being applied to healthcare, there is a need to
understand their effectiveness and strategies to design and implementation in order to accelerate
their utility and acceptance.

52
In their review to understand this, Demiris et al. (2019) categorized the use of
technological support to care givers into the following four functions: First, education and
service coordination. Second, delivery of caregiver specific cognitive behavioral interventions.
Third, delivery of clinical care. Fourth, peer support. Regarding education and service
coordination, information technology web-based tools known as home medication support for
home-based medicine are designed and implemented. Their application includes medication
schedules and calendar, tools for communication, conversion, and side effects. The delivery of
behavioral intervention is designed and implemented to assist caregivers in providing care
without having to travel to the patient in person. This is done through video conferencing of
telephone. Delivering of clinical care is performed through the use of telehealth platforms and
also using virtual systems that are web based. They have proven to work well in supporting care
givers and patients since they have the potential to connect with patients and their families in
their home. Peer support using information technology (e.g., social media and other online
services) has enabled patients with similar illnesses connect and share information. This also
supports the caregivers because of their ability to exchange information, connect and advise their
peers (Demiris et al., 2019). Demiris et al. (2019) stated that while health information technology
is beneficial, they also pose some challenges associated with accessibility, usability, privacy
maintenance and confidentiality, interoperability, accountability, liability, reimbursement, and
workflow changes.
According to Jusoh (2017), another form of innovative technology which continues to
grow towards health informatics is mobile technology. This kind of technology allows computer
operation from a device not connected to a physical link but to wireless communication. They
include smartphones, laptops, tablets, e-book readers, cameras, and the like. These mobile

53
technologies referred to as mhealth have been used by various healthcare organizations for
providing treatments, making treatment diagnosis, monitoring illness, promoting health self-
management and healthy lifestyles. Jusoh (2017) stated that mhealth has been applied to
supporting treatment of chronic illnesses with diabetes ranked as number one with the highest
expenditures in treatment and prevention. Using these tools has proven to be cost effective. Other
disease interventions mhealth supports are stroke, flu, gout, and bowel disease. These apps are
designed to assist caregivers and their patients.
Jusoh (2017) described mhealth apps as very useful tools to healthcare institutions,
communities, healthcare workers and most individuals, more especially those in developing
countries. They have the potential to provide quality care systems in the majority of emerging
countries through their support to community healthcare workers and they are some of the most
cost-effective methods of improving healthcare and saving lives. Jusoh (2017) stated that since
they are not grounded in theory, it is not convincing that they can provide substantial impact on
those who use them. There are other concerns related to addressing security issues and usability.
Jusoh (2017) asserted that in spite of some potential challenges or barriers, these innovative tools
have greater opportunities that still need to be explored.
According to Gandarillas and Goswami (2018), the health care industry has realized a
rapid growth in the adoption of information and communication technologies (ICT). These tools
are impacting health care delivery in numerous ways, most that are beneficial. However, also
poses challenges. The following benefits are highlighted by Gandarillas and Goswami (2018).
First, information and communication technology allow for powerful means of processing a
variety of data about numerous individuals in different locations. This has resulted in the
development of new and more effective methods of prevention and treatment. Second,

54
information and communication technology tools are allowing more autonomy and quality of life
for patients. Third, improvement in cost-efficiency of health facilities. Fourth, the promotion of a
new culture of interagency collaboration and public participation, which highly benefits patients
with a complex array of health problems and comorbidities.
In most cases, it occurs with older people with chronic diseases. Information and
communication technology tools have facilitated early disease diagnosis and prevention. Its
systems include noninvasive monitoring tools, gathering relevant patient’s health and wellbeing
information within predictive applications to be used by the patients and health facilities
(Gandarillas & Goswami, 2018). Health information technologies of this nature can incorporate
and process large amounts of real-time, various types of information from/to the patients’ home
and natural settings, as well as from/to different areas and agencies in shared, interoperable, and
big databases using cloud computing technology and information recording and processing
applications for smart wearable (Gandarillas & Goswami, 2018).
Despite all the benefits information and communication technology tools offer,
Gandarillas and Goswami (2018) stated that they also pose some challenges to both the patients
and the health care providers. Regarding the patients, the challenges include high dependence on
health care facilities, false expectations of protection, difficulties managing the technology,
increased isolation, excessive feelings of responsibility and blame, and false alarms created by
disease predictions. On the other hand, for health care providers, these challenges are comprised
of difficulties in protecting data and other issues related to the need to hire new staff, training,
and organizational restructuring. In order to maximize the effectiveness in the use of information
and communication technology tools, there is a need to address current trends approaches and

55
the implementation of a multitude practices that require analyzing, incorporating into emerging
tools and systems.
Challenges with the Use of Technology in Healthcare
Technological advances in U.S. healthcare system have contributed to scientific research,
the development of new treatments, higher training of healthcare professionals, establishment of
efficient facilities, equipment, and information technology (Shi & Singh, 2019). Although
medical technology brings about substantial benefits, there are also a number of challenges that
follow. One of the main challenges encountered in the use of medical technology has been the
cost associated with research and development, such as introduction and improvements of
products, development of new medical technology or state of the art machines, pharmaceuticals,
and biological therapies (Shi & Singh, 2019). The cost has also impacted health care information
systems such as electronic healthcare records, management and operational healthcare delivery
systems like E health and telemedicine (Shi & Singh, 2019). In addition, the author expressed
that the source of high health care costs does not solely come from the development of
technology, but also third-part payment systems, an increase in the elderly population, the use of
the medical model of health care delivery, multiplayer system and administrative costs, defensive
medicine, waste, and abuse.
Berliner (2014) stated that some of the factors which have led to the increase in the use of
health care advanced medical technology by medical doctors are financial incentives, pressure
from their peers to utilize new technology, and misuse of the technology; these have also
contributed to the increase costs in health care. With medical information technology, there are a
number of other challenges other than high costs. First, organizational barriers to effective use of
information technology; where at times, hospitals can experience some delays in accessing

56
patient information for medical delivery or treatment, especially if the patient’s information is
not in the EHR or not created in a timely manner (Carayon et al., 2012). Second, the lack of
health care IT being interoperable can lead to duplication of patient’s data and documentation.
Third, as in most industries, there is often a slow response time or network disconnection which
occurs when care managers have a number of information technology applications running at the
same time. Fourth, with regards to information technology training and knowledge, since the
healthcare providers have to work with various hospitals with different kinds of HERs, becomes
difficult for them to learn and remain proficient with each and every software. As such, they tend
to utilize the ones they are more familiar with (Carayon et al., 2012). Like clinical guidelines,
technology and scientific knowledge change more regularly making it difficult and
overwhelming for some physicians to keep with and incorporate it in provision of quality
healthcare (Tsugawa et al., 2017).
Balestra (2017) stated that healthcare organizations continue the adoption of health
information technology in order to realize benefits such as improved quality of patient care,
reduced costs, and increased efficiency. Despite such benefits, the use of health information
technology poses several ethical and legal challenges among nursing practitioners. First, the use
of technology can create barriers between patients and medical health practitioners. Secondly,
nurses face challenges when navigating such applications due to the rigorous data entry
requirements and complicated user interfaces. In addition, electronic health records increase the
risks of data breaches which can lead to a loss of patient privacy (Balestra, 2017). Because of
that, electronic health records can expose medical health practitioners to legal liabilities in
various ways. Such liabilities can arise from a failure to document all patient information, narrow

57
templates that do not include all the relevant information about diseases, and a lack of
consideration of clinical decision support (Balestra, 2017).
According to Balestra (2017), there are several strategies to deal with these ethical and
legal challenges. First, all healthcare organizations that use electronic health records must train
all their medical practitioners. Second, organizations must request written basic manuals for
operating the system. Additionally, health organizations must hold regular meetings with their
medical practitioners to examine the emerging challenges and ways of dealing with them. It is
critical to design and implement a policy that provides a framework for the programs in these
organizations. It is important to ensure that the adoption of health information technology in
healthcare organizations does not interfere with communication with patients. Medical health
practitioners must ensure that patients do not feel neglected. Rathert et al. (2019) agreed that
health information technology like EHR facilitates the efficient coordination of care delivery
among health care providers. Based on a survey they conducted on primary care medical
providers, Rathert et al. (2019) suggested that the full potential benefits of electronic health
records have not yet been realized due to some of the challenges cited. They included the
following: (a) increased workload on clinicians, (b) provider overreliance on health information
technology, (c) interference with interpersonal relationship, (d) inadequate EHR training, and (e)
lack of trust of EHR information.
The increased workloads arose due to factors such as time delays resulting from data not
being inputted in a timely fashion and having to make calls to track patient information, rework
due to insufficient data on patient encounters and too much information that needs to be captured
(Rathert et al., 2019). Regarding overreliance on EHR, often times, clinicians could not make
sound clinical decisions as it posed risk and inaccuracy in situations where access was lost due to

58
the going offline suddenly. Rathert et al. (2019) stated that the interference with interpersonal
relationships stemmed from the real time requirements of EHR because it made clinicians feel
that it was replacing their in-person care delivery. Inadequate training on EHR impacted the
clinicians’ ability to communicate and coordinate efficient care and lack of trust was attributed to
some inaccuracies in the data entered, unclear notations and delayed data entry.
According to Carayon and Hoonakker (2019), in today’s market health care organizations
worldwide are substantially investing in the design and implementation of modern health
information technology such as clinical dashboards, status displays, clinical decision support and
other patient facing technologies. The implementation of such technology can lead to positive
outcomes in health care delivery. However, Carayon and Hoonakker (2019) stated there are
some challenges with health information technology related to useability and human factors.
These problems extend to other clinicians including nurses, nursing leaders, information
technology expects engineers, other human factors, and patients. If not effectively addressed,
these challenges can lead to negative outcomes which can be harmful to the patient, frustrate the
clinicians and adversely impact their performance.
From their analysis on the study, they conducted on the impact of health information
technology and safety, Carayon and Hoonakker (2019) stated that medication safety events
revealed that about a third were associated with electronic health records useability issues. The
problems included medication events either with orders missing or being duplicated.
Additionally, their analysis of a study concerning the impact of health information technology
useability on clinician’s quality of working life revealed the following: unmanageable demands
for documentation, poor health information technology useability and workflow integration

59
issues. Such challenges negatively impacted the clinician’s quality of working life (Carayon &
Hoonakker, 2019).
Kruse et al. (2016) stated that while the adoption and implementation of electronic health
records system has substantially increased, there are still hospitals and health care organizations
facing barriers and challenges in its adoption due to numerous reasons. To mention but a few,
they are as follows: (a) high initial cost, (b) lack of technical support, (c) resistance to changing
work habits, (d) high maintenance ongoing costs, (e) insufficient training, (f) privacy concerns,
(g) time consuming, (h) workflow challenges, (i) lack of financial incentives perceived
usefulness, (j) inability to easily input historical medical record data, (k) return on investment
uncertainty, (l) lack of clarity of federal and state policies, (m) cost of penalties, (n) lack of user
acceptance, (o) complexity of systems, (p) medical errors, and (q) lack of sufficient staff.
Palabindala et al. (2016) stated that while electronic health records systems are not new to the
health care industry, their adoption have been tremendously slow. The slowness is attributable to
several challenges such as lawsuits and legal complications, increased risk of medical error and
implementation cost. According to Palabindala et al. (2016), poor implementation of electronic
health records can increase the risk of error, which will expose physicians and hospitals to
potential medical malpractice lawsuits and other legal complications. Medical error, adverse
patient events, and mortality can increase when a new EHR system is adopted incorrectly.
This can occur through an increase in user error as information is entered into a health
information system, they are not knowledgeable with and other electronic health records system
crashes that create problems in care delivery (Palabindala et al., 2016). Palabindala et al. (2016)
suggested that increased risk of medical error records by clinicians can occur due to the
clinician’s high reliance on electronic health records. When this occurs, it can negatively impact

60
clinical decisions and lead to medical errors. Other common actions made possible through the
electronic health records system, such as copy and paste, may cause a typographical error to be
copied repeatedly. Thus, resulting in a multitude of mistakes that could potentially lead to a
medical error that can harm the patient (Palabindala et al., 2016).
Another challenge that Palabindala et al. (2016) stated is one of the major factors
contributing to the unsuccessful adoption of EHR systems is the cost of implementation. This is
partly because it is still not clear where the primary payer is, however, the health care payers
reap most of the benefits associated with its use (Palabindala et al., 2016). Health care
organizations incur additional costs associated with regular system upgrades, ongoing
maintenance, and the need for hospitals to add EHR systems to their operations.
To address these challenges and succeed in EHR implementation, Palabindala et al.
(2016) suggested that hospital administrators and physicians must continuously investigate all
the potential risks for medical error, system failure, and legal responsibility before adopting the
systems. There will be an assurance that physicians are aware of their responsibilities with their
care delivery. Detailed information available within an EHR system is important for minimizing
the risk of malpractice and lawsuit. Lastly, it is imperative that hospitals commit to regular
system upgrading and required training for all users to reduce the risk of medical errors
(Palabindala et al., 2016).
According to Koppel and Kuziemsky (2019), health information technology usability
challenges continue to exist as its adoption continues to grow and accessible to various medical
providers. These challenges as described by Koppel and Kuziemsky (2019) can be classified in
the following three categories: (a) displays, navigation, and screen rules; (b) implementation,
staffing, and cost; and (c) authentication, staff access rules, and logins/logouts.

61
Displays, navigation, and screen rules pose challenges because different EHR systems
and versions present data in different ways. This often results in inconsistent and confusing data
displays and high variability in terms of fonts, colors, metrics, and interfaces. Additionally, there
is a high level of navigation inconsistency related to patient data searching and functions to
locate clinical data (Koppel & Kuziemsky, 2019). These types of issues can result in
inefficiencies in care delivery and harm the patient.
Implementation, staffing, and cost challenges, according to Koppel and Kuziemsky
(2019), arise from conflicts between the medical staff and their organizational leadership or
corporate selected consultants. These conflicts occur due to reasons related to EHR
implementation authority concerning where is it within the organization or by the enterprise.
Other reasons are due related to the role of the consultants in the implementation regarding
whether they are in control of system configuration or advisory. These issues can determine the
cost of EHR design, cost, and implementation (Koppel & Kuziemsky, 2019).
Authentication, the staff access rules, and logins/logouts challenges are caused by the
required repeated logins and complicated authentications since they can often result in increased
workaround frustration and errors (Koppel & Kuziemsky, 2019). Koppel and Kuziemsky (2019)
stated that they can create opportunities for unauthorized access and are inconsistent with clinical
need and workflow are a major frustration and lead clinicians to share passwords and ID cards.
Coordination of Health Care with Health Information Technology
The use of Electronic Health Records (EHR) has changed the way doctors communicate
with patients to examine or diagnose their illness; unfortunately, often it has resulted in patient
misdiagnosis (Towery & Hough, 2018). Traditionally medical doctors are trained to spend more
time communicating and listening to the patient in order to ascertain what is wrong with them.

62
Since the evolution of EHR, it is estimated that doctors spend the majority of the time on the
system and very little with the patient (Towery & Hough, 2018). Because of that, there has been
some patient misdiagnosis resulting in major costs overrun to the health care organization and
the patient (Towery & Hough, 2018). Meskó et al. (2017) asserted that doctors are not using
EHR efficiently in their diagnosis of the patient because they spend more time reviewing patient
data on EHR rather than paying attention to the patient and thereby leading to the loss of
personal touch with the patient. As such, they suggest that information technology does not
satisfactorily cover the whole process of treatment which includes empathy, proper
communication, and human touch (Meskó et al., 2017).
While information technology such as EHR are very useful in healthcare, it cannot
replace the personal connection and trust it gains from human capital (Meskó et al., 2017).
According to Shi and Singh (2019), the use of electronic medical records by the physicians has
resulted in timely access to the patient’s records, alerting them of potential errors and making lab
values ready when needed. With the personal health records system, patients are able to access
their own health information while aiding them to manage their own health. The system also
allows patients to interact with their providers electronically at various locations including their
own homes. Personal electronic records system has benefited more of the patients with
disabilities or limited mobility; and older patients with chronic disease have gained better
coordination for preventative care (Nimkar, 2016). Information technology education covers
health help that educate patients in the self-management of their chronic conditions, prevention,
treatment adherence, health related communication, data collection, remote monitorization and
continuous education to the providers. It has also contributed to the drastic improvement in the
accessibility and availability of health information.

63
Information technology has also enabled the use of social media in health education; as
such numerous healthcare organizations are using social media to publicize their health services
and provide up- to-date health information to both their current and prospective patients
(Nimkar, 2016). Other benefits as suggested by Shi and Singh (2019) are E-Health and E-
Therapy. E-Health, which is known for all forms of electronic healthcare delivered over the
internet, ranging from informational, education, and commercial products. With this technology,
providers have been able to create secure internet portals which allow the patient to access their
record; enabling both the provider and the patient to exchange email and text messaging through
smartphone mobile apps and tablets. The E-health has not only benefited the patients as a source
of information and communications, but it has also been used for the checking in process such as
registering patients online and directing them to alternative care site as well as transmitting
diagnostic results (Shi & Singh, 2019).
E-Therapy, which is also known as online therapy, e-counselling, teletherapy or cyber
counselling has also been effective in the coordination of treating psychosocial health issues.
With E-therapy, the patient is able to receive health care with the use of interactive websites
(Christensen & Petrie, 2013). According to Shi and Singh (2019), telemedicine,
telecommunication is used in the diagnosis and patient care in cases where the provider and the
patient are at separate distance locations. Telemedicine allows the general physician to consult
the specialist on complicated diagnosis. Remote monitoring programs such as the use of blood
pressure and blood glucose monitoring system have contributed to the cost-effective way of
helping the patients monitor their health continuously; and it also aided in the detection of major
issues early enough to reduce major complications. Additionally, remote monitoring devices

64
such as pacemakers have increased in use and the patients are satisfied with the results; and
thereby reducing their hospital visits (Shi & Singh, 2019).
According to McCormick et al. (2012), providing physician access to prior imaging tests
reduces some unnecessary tests, especially for the expensive advanced imaging. The improved
availability of electronic data from the previous physical examination and diagnosis does provide
some assurance that the current health care issue is stable, hence there will be no need to conduct
further tests. The authors suggest that electronic point of order decision supports the provision of
real time feedback on imaging, thereby reducing tests and unnecessary procedures (McCormick
et al., 2012). Using electronic healthcare records and computerized provider order entry systems
have resulted in some potential interventions which could interrupt and reduce duplicate
healthcare services before they are performed (Lofthus et al., 2015).
Saillour-Glénisson et al. (2017) stated that health information technologies are effective
tools with the potential to improve information systems between health care and social care
professionals as well as between patients and health care professionals. In so doing allows better
access to more detailed information necessary for improving communication and coordination
between health care and social care organizations as well as health care professionals. Health
information technology tools provides centralization of all patient management information,
creation of shared tools for healthcare coordination, creation of alerts, feedback, reminders thus
supporting the coordination of health and social care professionals and patients in their care
process, continuous quality assessment and care efficiency as well as the development of a
shared culture between professionals (Saillour-Glénisson et al., 2017). According to Falconer et
al. (2018), benefits of care coordination using health information technology are realized in most

65
areas, including screening, scheduling assessments, accessing patient information, facilitating
communications, and improving treatment compliance.
Electronic health records can foster coordinated care with real-time information that
allows health care providers to update patient health information promptly and distribute it to
other authorized providers in disparate care areas such as mental health care (Falconer et al.,
2018). Other systems such as web-based communication tools can help in coordinated decision
making and patient-provider communication by offering a means for patients to establish goals,
view test results, and medications, and identify care team members. Falconer et al. (2018)
asserted that the general use of health information technology has positively promoted the
management of mental health care, and technology can be used not only for collaborative efforts
but also to aid patients with compiling with medication and chronic disease management.
Health Information Technology Privacy and Risk
With the emergence and digitalization of EHRs, as has been discussed earlier, growing
concerns continue to develop surrounding the privacy of personal information. These
apprehensions have created turbulent unrest in the minds of patients. It is pertinent to note, that
because of these primary concerns, all health care providers have been compelled to adhere to
the Health Insurance Portability and Accountability Act (HIPAA), a United States legislation
that provides data privacy and security provisions for safeguarding medical information
(Vanderpool, 2019). Today’s ever increasingly digital age is showcasing volumes of personal
information captured in electronic databases. These new developments have continuously
instilled growing concerns and fears among patients, health care providers and the public at
large. It is worth noting though that not one day passes without a news headline announcing a
major privacy breach or cybersecurity attack on personal information (Sheikh et al., 2022).

66
Yüksel et al. (2017) acknowledged that electronic health services are increasingly being
used in health care by patients, providers, employers, doctors, policy makers and other healthcare
workers to reduce cost and provide efficient healthcare. States that the use of electronic health
services raises many concerns surrounding security, privacy, and the integrity of patient’s
healthcare data. Such concerns impact the patient’s willingness to disclose their healthcare data
and can result in harm to the patient (Yüksel et al., 2017). According to Yüksel et al. (2017), the
basic elements of electronic health services consist of patient healthcare professional and data
storage in privacy situations.
To guard against privacy, patient data can be encrypted and stored in cloud storage
servers. Other methods include using access and control techniques to limit and prevent
unauthorized parties. In cases of emergency care, health data may not be used for the patient and
therefore emergency authorization would need to be addressed through systems such as smart
cards, biometric and other trusted parties. According to Kruse et al. (2017), the most critical
barriers to the adoption of electronic health records are associated with privacy and security
concerns. Kruse et al. (2017) described electronic health records as an information system that
contains a patient’s medical history and is maintained by medical providers’ overtime. Such
information also includes administrative clinical data related to the patients in the form of
demography, medical issues, vital signs, immunization, and the like. Because of the sensitivity of
this information, several regulations have been established for safeguard (Kruse et al., 2017) to
mention but a few, Health Insurance Portability and Accountability Act (HIPAA), Health
Information Technology for Economic and Clinical Health Act (HITECH), and the
Confidentiality and Security of Protected health information (PHI). According to Kruse et al.
(2017), HIPAA is comprised of three pillars namely, administrative safeguards, physical

67
safeguards, and technical safeguards for health care. The address issues such as the location of
computers to the usage of security protection. HITECH enforces the reporting of any data
breaches by health care organizations. Kruse et al. (2017) stated that in spite of the availability of
numerous security techniques, it is hard to determine which once are suitable due to the
continuous increase and sophisticated cyber threats which can impact the security of electronic
health records. This could depend on the size or scope of the health care organization.
Meinert et al. (2018) agreed that technology can potentially provide s the implementation
of a value-based healthcare system, which the impacts of quality of care is being offered at
optimized cost for greater benefit of the benefit. Technology can offer value by aiding in data
collection used for the evaluation and measurement outcomes. According to Meinert et al.
(2018), healthcare organizations face some challenges and risks that result from exclusive use of
most of the health information technologies. These challenges are associated with their
unsustainability, due to lack of scale up plans and timely evaluations. Other risks include
noncompliance with data protection policies, inadequate data governance, and overestimated
expectations resulting from the rapid introduction of new technologies (Meinert et al., 2018).
They also subject systems to new risks and challenges. It is widely believed that key challenges
with health technologies is not only its design or the innovation, but the lack of policies and
frameworks that can enable its adoption, sustainability, and its capability to be used in a wide
range of functions in healthcare (Meinert et al., 2018). Other challenges of significant concern in
creating value base innovation are associated with security and privacy.
This is worrisome because an increase in data collection and sharing creates patient
privacy concerns due to the potential of unintended use digital systems can be subject to non-
compliance with information governance regulations, data breaches and cyber-attacks (Meinert

68
et al., 2018). According to Meinert et al. (2018), because of the increase in storing and sharing of
patient data, it is critical for organizations to have a high level of cybersecurity maintenance.
Cyber-attacks occur when outside or inside entities system interfere with the networks in order to
access the organization’s systems. Healthcare organizations hold a substantial amount of data in
a wide array of resources as they strive to create value-based systems. Healthcare organizations
strive to do so through the use of technology and encounter some challenges and risks in the
process. It is imperative that their impact on the value-based systems be addressed otherwise
their impact benefits could be overestimated and benefits be reduced considering the changing
circumstances (Meinert et al., 2018).
Due to healthcare organizations size and complexity, there is a major challenge
surrounding realistic goals and timelines while managing the eminent change needed for existing
individuals, systems, and processes (Meinert et al., 2018). These risks do not suggest that the
need for technology should not be pursued, or quality can should be pursued without it.
Technological engagement in healthcare is inevitable. Meinert et al. (2018) suggested that with
the increase in the adoption of healthcare technologies and that numerous other industries are
benefiting greatly from it, there is a strong need to identify the risks and challenges related to it
and find strategies that can help mitigate the risks and challenges. In this way, healthcare
organizations can utilize them efficiently and continue to gain the maximum benefits.
According to Shi et al. (2020), considering health care science developed and the
emerging management concepts, management of the healthcare field continues to receive greater
attention. This is surrounding healthcare issues like health care quality, doctor-patient
communication, and patient information. The other part of health care management has evolved
from traditional to more innovative, which makes health care digitization the trend of the times.

69
Shi et al. (2020) suggested that health information technology development has been adopted
worldwide. Health information technologies such as telemedicine and smart health care have
become dominant fields in the health care industry. With these developments, health care
facilities are faced with growing care data resulting in information security issues as well as
privacy a major problem (Shi et al., 2020). According to Shi et al. (2020), what drives the
transformation of health care is big data in health information technologies such as electronic
health care records, pictures, clinical test data and the like. With the use of big data into the
health care field, there are challenges stemming from using traditional software or hardware to
manage large and complex health care information (Shi et al., 2020).
The reason being that the information leakage in the health care big data environment is
not only the data itself, but more serious as the hacker can steal patient’s information such as
their social security number, health data, personal finance, and the like through mining the
hidden information behind the data and endangering patients’ personal and property safety and
even bringing serious moral and ethical issues to the health care organization (Shi et al., 2020).
Healthcare management is centered around humans and based on healthcare organization matters
related to internal resources, management operation and service. Shi et al. (2020) stated that it
also involves the security management of patient related information. Such security management
requires the development of the cloud platform because it provides the management capability
for large scale health information and reduces the cost of management.
Sadoughi and Erfannia (2017) described cloud computing as one of the newest
technological advancements that has tremendous impact on various spheres of knowledge. It is a
new computer model providing service. Some of the advantages of cloud computing as stated by
Sadoughi and Erfannia (2017) included the following: First, it can host different sources of

70
information by creating an integrated platform. Second, such integrated information platforms
provide suitable data analysis and model discovery opportunities in health sciences. Third, its
storage through the property of service providing payment significantly decreases
implementation and manpower costs associated with the successful realization of health
information technology, which leads to the enhancement of financial savings in healthcare.
According to Sadoughi and Erfannia (2017), the increase in the volume of medical data and the
associated restrictions on the storage and maintenance of this data, requires the use of systems
with high volume data storage tanks such as cloud computing, hence, health care providers must
provide telemedicine services through cloud computing. Health care providers have made
electronic files the necessary tools as the focus for implementing cloud computing because
electronic health records technology and cloud computing will enhance the quality of medical
services (Sadoughi & Erfannia, 2017).
Because cloud computing facilitates the successful implementation of electronic records,
organizations are more likely to cooperate and invest in it. There are some challenges it poses
such as the possibility of interoperability between systems which creates problems of
transforming electronic data (Sadoughi & Erfannia, 2017). According to Sadoughi and Erfannia
(2017), other challenges include hardware limitations in storing and maintaining health data,
slowed down data access due to the increased volume of stored data, security issues, privacy, and
data backup, as well as sharing health information which has been traditionally stored. Sadoughi
and Erfannia (2017) suggested that these challenges could be solved by standardizing health
information before migrating it into the Cloud and integrating related data. Sadoughi and
Erfannia (2017) stated that even though it appears that cloud computing can overcome some of
the barriers that health information systems are faced with. Various systems such as electronic

71
health records have not been fully analyzed. To address the problems associated with health
information systems and considerations of cloud computing, reviewing related information
would be helpful.
Physician’s Burnout Related to Health Information Technology
According to Heponiemi et al. (2017), traditionally most of the stress on the job amongst
physicians been caused by time pressure, workload, difficult patients, and problems in teamwork.
Another form of stress has been caused by information technology because of the following:
Poor functionality, more time consumption, and inadequate information. Heponiemi et al. (2017)
stated that use of information technology has resulted in the increase of physician’s workload
and cognitive demands. Another factor causing the stress with the physicians’ use of information
technology is related to the increased functions in electronic health records (Heponiemi et al.,
2017). Time pressure associated with the utilization of information technology has greatly led to
some negative outcomes such as burnout, dissatisfaction, and high turnover among the
physicians who had to manage a high number of electronic health records functions compared to
those managing a low number of functions (Heponiemi et al., 2017).
According to Heponiemi et al. (2017), there are several other issues that physicians lack
of satisfaction with electronic health records. They are as follows: First, poor electronic health
records usability. Second, time-consuming data entry. Third, its interference with face-to-face
patient care. Fourth, the inability to exchange health information between health information
systems and most prominently, impairments in clinical documentation. To illustrate why the
adoption of health information technology is associated with some negative impact amongst
medical practitioners, Heponiemi et al. (2017) used a longitudinal used a longitudinal design to
collect data from a random sample of Finnish physicians. The study indicated that the use of

72
such technologies increased psychosocial pressure measured by stress among the respondents.
The study showed that such pressure increased over time. Using health information technologies
lowered the time spent delivering care. The research indicated that stress related to the use of
health information technology was higher among physicians in leadership positions.
The researchers indicate that psychosocial stress can complicate the implementation of
technologies due to the accompanying strain and stress. The research reveals that private
practitioners record lower levels of stress associated with the use of health information
technologies. Gardner et al. (2019) agreed that stress associated with health information
technology greatly affects physicians and it also affects their patients and overall, the health
system, other than high rates of turnover. Physicians who are stressed out engage in other
negative behaviors such as substance abuse which can result in malpractice due to medical errors
(Gardner et al., 2019). Their patients can suffer for lower satisfaction with their care and
experience more test orders and unnecessary consultation. Healthcare organizations tend to bear
major costs associated with this burnout as it also impacts productivity.
Gardner et al. (2019) stated that in order to effectively address the issues of the burnout
associated health information technology on physicians, healthcare organizations must treat
burnout as an important workforce metric and identify factors which contribute to it. While there
are many other factors such as chaotic work environment, lack of alignment between doctors’
values and the organization’s leader, time and productivity, the role of health information
technology in physician’s burnout is not well defined (Gardner et al., 2019). Physicians attribute
their burnout to the use of electronic health records because they are dissatisfied with the notion
that it is meant to reduce clinical hours (Gardner et al., 2019). They feel that it poses challenges
related to efficient navigation, additional time to execute documentation in it and the increased

73
number of clerical tasks such as data entry they have to do. Gardner et al. (2019) suggested that
once health care organizations have identified the opportunities to deal with health information
stress, they can implement systems such as evidence-based interventions to address the issues.
Some of the potential interventions would include scribes, team-based documentation performed
by medical assistance and continuous training on electronic health records.
According to Vehko et al. (2019), the increased use of information technology and
communication technology has been associated with high time pressure and stress on medical
personnel. In the study they conducted in Finland on registered nurses, Vehko et al. (2019) found
that factors such as unreliability and low user friendliness of electronic health records were major
sources contributing to time pressure and psychological issues among clinicians. Other than that,
other factors included low e-care competencies and low support for cooperation (Vehko et al.,
2019). To effectively address these factors, Vehko et al. (2019) suggested that health care
organizations need to have user friendly EHR systems and digital tools as well strengthen the
clinicians e-care competencies through organizational and regional actions. Poon et al. (2021)
concurred that health information technology has been identified as one of the factors
contributing to clinician burnout. Other than not being user friendly, electronic health records
poses issues associated with not being able to meet billing and regulatory requirements.
Other important causes of stress are due to high clinical volumes, an increase in hyper
specialization among clinicians and some mismatch arising from incentives driving system
design, buyers and much more (Poon et al., 2021). To mitigate the burnout, Poon et al. (2021)
suggested the need for innovative solutions. To mention but a few: First, innovative solution that
would require electronic health records to recognize the need to partner with informatics
innovators to advance usability. Second, to spread and sustain usability innovations arising from

74
an individual customer across the base. Third, offering personalized customization and training
sessions as they would lead to improved self-reported efficiency and reduce stress. Kroth et al.
(2018) stated that while health information and communication technology has benefited health
care organizations tremendously, it has also resulted it personal and professional consequences.
With that being said, Kroth et al. (2018) suggested the need to redesign health
information and communication technologies as well as the clinical and architectural process in
order to realize significant improvements. High stress levels and burnout impact physicians’
health, ability to perform professional work and quality care for the patient (Kroth et al., 2018).
In a study the conducted on a focus group of ambulatory physicians, Kroth et al. (2018) derived
the following findings related to the burnout assessment associated with the use of current
electronic health and communication technology: (a) excessive data entry requirements, (b) user
interfaces with inefficient design, (c) insufficient health information exchange from external
institutions, (d) information overload, (e) interference with patient physician relationship, and (f)
ergonomic problems. Because of these issues, physicians are confronted with high levels of
stress and burnout as well as being unable to take control of their work efficiently (Kroth et al.,
2018).
Furthermore, they face physical challenges due to ergonomic problems. These problems
include eye strain, neck, wrist, and shoulder pain. Participants noted some benefits associated
with health information and communication technology (Kroth et al., 2018). They included
having the data they needed in a more centralized location; being able to access data from
multiple sites and connect with other clinicians, other benefits included improved
communication with patients and improved quality care (Kroth et al., 2018).

75
According to Kroth et al. (2018), there are several solutions that can be taken to
overcome some of these challenges. They include the following: First, using architectural design
that meets modern health care workflow and the reduction of the number of various chairs and
workstations. Second, offering occupational and physical therapy. Third, using scribes to reduce
data entry or having support staff to handle the data entry in the electronic record. Medical
scribes have the potential to provide substantial in physician’s satisfaction and increase
productivity with the support staff handling the bulk of the data entry helps the physician focus
on the patient and thus enhances patient physician relationship (Kroth et al., 2018). Other
solutions include providing electronic health records training on a periodical basis, improving
user interface design, and having greater interoperability (Kroth et al., 2018). According to
Bakken (2019), the design of innovations can be used to improve clinician’s performance in
some of the common tasks they engage in when utilizing electronic health records. For instance,
automating the retrieval and reconciliation of information across multiple electronic documents
has the potential to reduce the clinician’s workload and its complexity, thus resulting in reduced
stress level. Bakken (2019) argued that the design of innovations alone cannot solve the burnout
issues. Other factors such as organizational culture, health care marketplace, technology
ecosystem and national policy must also be taken into consideration.
Anticipated and Discovered Themes
The following themes were derived from the review of the literature: (a) quality and
patient safety, (b) electronic health records technology, (c) health information technology and
efficiency in care delivery, (d) innovative health information technology, (e) challenges with the
use of technology in health care, (f) coordination of health care with health information
technology, (g) health information technology privacy and risk, and (h) physician’s burnout

76
related to health information technology. Most of these themes and sources from the literature
discussed similar issues associated with health information technology. Even though the are
some similarities in most of them, the volume of their content is different.
Quality and Safety
Magrabi et al. (2016) stated that health information technology offers a wide array of
benefits for quality care. If not implemented and managed efficiently, it can affect quality and
safety. Kim et al. (2017) agreed and also stated that the increase in its adoption has benefited
health care tremendously. If not adopted efficiently, it can lead to a disruption in quality care and
lead to patient harm. Sittig et al. (2018) also agreed but cautions about some challenges health
information technology can pose without safe design, development, implementation, and
usability. Other concerns that were raised by Adams et al. (2017) and Alotaibi and Federico
(2017) are levels of interoperability, because without them, patient safety can be impacted. To
fully explore the use of health information technology for the provision of quality care, Feldman
et al. (2018) stated that it is critical to understand the implementations being used by other
organizations relative to quality human resource planning, cost management and outcomes.
Electronic Health Records Technology
Fong et al. (2017) stated that many hospitals are using electronic health records
technology to support their clinical functions. While this has resulted in positive health
outcomes; if not well designed, developed, implemented, and used efficiently, they can result in
serious safety issues. Wani and Malhotra (2018) suggested that proponents of electronic health
records believe that it has helped health care providers increase productivity and incur fewer
errors in patient diagnosis and treatment, hence, the end result of efficiency in health care
delivery. Shi and Singh (2019) stated that it has enabled clinician’s research and management of

77
various health issues. Chao et al. (2013) echoed that electronic health records have tremendously
contributed to the provision of timely and quality care because it has enabled health care
providers to monitor patient care and progress more efficiently.
Health Information Technology and Efficiency in Care Delivery
Hossain et al. (2018) concurred that health information technology facilitates the use of
devices to promote quality care. Their use is more cost effective in monitoring health care. There
is a high potential as identified by stakeholders that they can reduce health care costs and
improve care. Huang et al. (2017) added that advances in health care technologies related to
imaging have accelerated the timely diagnosis of early childhood cancers. With timely diagnosis,
continuous monitoring, and appropriate treatment. Technology has facilitated the improvement
of outcomes within health systems as stated by Huang et al. (2017). Hossain et al. (2018) stated
that such improvements include the encryption and decryption features the electronic systems
provide to guard against security. This has allowed data storage and protection at a lower cost.
Sood and McNeil (2017) stated that to continue to maximize the efficient use of health
information technology, stakeholders must take into consideration their workforce, more
especially concerning restructuring workflows and processes as technology is continuously
evolving.
Innovative Health Information Technology
Anderson et al. (2017) described innovative health information technology as an enhance
care management support system designed to enable patients to gain better outcomes at a
reasonable cost. They are made up of a number of applications that include operational data
which can be accessed by various clinicians concurrently. These technological systems have
benefited high risk patients. Salway et al. (2020) stated that by employing innovative health

78
technologies, such as smart tables and dashboards, New City York Health + Hospitals were able
to gain a better handle on some challenges with delivering care to COVID-19 patients. Rudin et
al. (2017) agreed that the use of innovative technologies help in addressing the coordination of
health care for complex patients. However, states that there are challenges concerning their
functionalities due to lack of interoperability between coordinating systems. Demiris et al. (2019)
stated that since there is an increase in the use of these innovative solutions, there is a need to
understand their effectiveness and strategies to design and implementation. They are beneficial
in delivering care to various geographic environments.
Challenges with the Use of Technology in Healthcare
Shi and Singh (2019) stated there are a number of challenges associated with the use of
health information technology, with the main one being the cost of research and development.
Such costs have also impacted the management of health information systems such as electronic
health records and telemedicine. Challenges cited by Rathert et al. (2019) are attributed to
numerous factors such as the increased workload on clinicians, lack of sufficient training and
trust of electronic health records information as well as the interference of interpersonal
relationships between patient and provider. Other challenges include organizational barriers to its
effective use, delays and even disruptions which can affect the timely access to patient
information. Balestra (2017) stated that technology also poses ethical and legal challenges which
can result from the risk with data entry and storage.
Coordination of Health Care with Health Information Technology
This theme discusses how electronic health records and other health care information
technologies have transformed the delivery of care. Towery and Hough (2018) acknowledged
that points out that because of how it has changed the way doctors communicate with their

79
patients, it can often result in patient misdiagnosis leading and lead to patient harm as well as
major costs. Meskó et al. (2017) agreed that health information technology does not coordinate
health care efficiently because physicians are not using it appropriately. However, Shi and Singh
(2019) stated that the use of electronic health records has increased efficiency because doctors
can access health information in a timely manner. Nimkar (2016) added that it has also benefited
the coordination of care for patients with disabilities and other chronic illnesses.
Health Information Technology Privacy and Risk
Vanderpool (2019) stated that the use of electronic health records raises some concerns
related to privacy of personal information. Yüksel et al. (2017) agreed and stated that it also raise
concerns about security and integrity of patients’ health information. To guard against that,
Yüksel et al. (2017) suggested that patient data be encrypted and stored in cloud storage servers.
Other risks cited by Meinert et al. (2018) included unsustainability, noncompliance with data
protection policies, and inadequate data governance.
Physician’s Burnout Related to Health Information Technology
Heponiemi et al. (2017) stated that recently another form of stress physicians have been
experiencing is attributed to health information technology because of poor functionality, more
consumption and insufficient information. Additionally, the increased functions in electronic
health records and the pressure associated with its use. Such stress has led to burnout,
dissatisfaction, and high turnover amongst physicians. Gardner et al. (2019) agreed there is stress
associated with the use of health information technology and adds that it affects patients and the
health care system. When feeling stressed out, physicians often resort to other negative behaviors
such as substance abuse which can lead to medical errors. To address this issue, Gardner et al.
(2019) suggested using interventions such as scribes, team-based documentation, and continuous

80
training on technology. Kroth et al. (2018) also suggested other interventions such as the need to
redesign health information and communication technologies as well as the clinical and
architectural process.
Summary of Literature Review
The review of the literature revealed that health information technology has impacted the
delivery of health care in an efficient and effective way. The themes captured in the review
illustrated that when adopted, developed, implemented, and used efficiently, health information
technology can lead to numerous benefits. To mention but a few, first, it can result in better
coordination of care delivery. Second, improve quality and efficiency. Third, with the
development of innovative health information technology, high risk diseases can me managed
effectively. Fourth, it has helped health care providers increase their productivity and incur fewer
errors. Fifth, it has made it possible to administer health care to various locations in a centralized
system. Despite the numerous benefits health information technology offers, there are challenges
associated with it and can affect its efficiency. These include high costs related to research and
management, interoperability issues, occasional delays which can affect care delivery. Other
challenges are concerns related to managing privacy and risk to ensure safety. Addressing
privacy and risk would require the encryption of data and using cloud data storage. The literature
review revealed that physicians often experience stress due to certain tasks applied in the use of
electronic health records. This burnout can lead to medical errors which will cause harm to the
patient. Addressing this issue would require interventions such as scribes, supporting assistants
and continuous training on medical records.
Based on the literature review the researcher discovered various perspectives associated
with health information technology. This review helped the researcher understand what direction

81
to follow in conducting this study, more especially the issues associated with ensuring the
efficient management of health information technology from areas of efficient design,
development, implementation, and usability as well as training, stress management and clinical
work redesign to accommodate the successful management of health information technology.
Summary of Section 1 and Transition
The purpose of the study was to explore and understand management issues surrounding
health information technology within the health care industry resulting in a disruption in the
provision of quality care delivery that can negatively impact business reputation. Section 1
provided the following key components for the study: introduction to the study, the background
of the problem, the problem statement, the purpose statement, research questions, nature of the
study, conceptual framework, the definition of terms, assumptions, limitations, delimitations, the
significance of the study, reduction of gaps in the literature, the implication to biblical
perspective and benefits to business practice and relationship to cognate. The background of the
problem and problem statement discussed benefits associated with the efficient use of health
information technology as well as the management issues that can result in problematic
outcomes. The research questions provided sought to find answers to the problems associated
with the subject matter. The nature of the study described the methodology that would be used to
conduct the study. It included the discussion of the research paradigm, method, and design. The
conceptual framework discussed the elements included in the research framework as they relate
to the problem statement. The definitions of terms and some of the frequently used terms and
acronyms in health information technology are provided. Assumptions, limitations, and
delimitations associated with the study are discussed. What makes this study significant is
discussed as it relates to the reduction of gaps in literature, the implication of biblical integration

82
and benefits to business practice and relationship to cognate. The reduction of gaps in the
literature is provided to illustrate that there is still much open for the study in the subject matter.
The implication of biblical integration was discussed to demonstrate and reinforce the
significance of this business research as a means of advancing God’s purpose for business on
earth. The benefit to business practice discussed that when used efficiently, health information
technology can result in business success. Additionally, Section 1 provided a detailed review of
the literature review outline on the numerous benefits of health information technology to
business practice. They included efficient and effective health care delivery, productivity, cost
reduction, research acceleration, proximity, and many more. The literature also indicated that if
not managed efficiently, health information technology can result in some undesirable outcomes
that can lead to the disruption of quality care delivery and impact negatively impact the business.
The literature review provided a number of possible causes of the inefficient management of
health information technology which included issues with interoperability, lack of efficient
design, development, adoption, implementation, and usability. To address these issues, the
literature also highlighted some possible solutions which included training, user acceptance,
leadership, and the like.
In Section 2, the researcher provided a detailed description of the study, the researcher’s
role as a researcher, the justification of the method, design, population, sampling, sampling, and
data collection techniques to be used in the study. Additionally, the researcher stated how data
will be organized and maintained as well as techniques that will be applied to ensure its validity
and reliability.

83
Section 2: The Project
In this section, the focus of this qualitative single case study was to discuss the project.
To do so, the researcher first provided the purpose statement. Second, discussed the role of the
researcher concerning actions to take in conducting the study, including the discussion of
bracketing as a means of avoiding personal bias in the research process. Third, a detailed
description of the research methodology to be used and its appropriateness to this study was
provided. Fourth, who the eligible participants are, the population, and the sampling are
explained. Fifth, how the data will be collected and organized was discussed. Sixth, the data
analysis process concerning emergent ideas, coding themes, interpretations, data representation,
and analysis for triangulation were discussed. Lastly, the researcher discussed reliability and
validity, including concepts such as credibility, transferability, dependability, and confirmability
for reliability and bracketing, triangulation, and saturation for validity, and then concluded with a
summary of Section 2.
Purpose Statement
The purpose of this qualitative single case study was to identify and discuss issues
surrounding the inefficient management of health information technology as they affect the
delivery of quality health care, resulting in a negative impact on the organization’s business
reputation (Gauthier et al., 2018). The study assessed steps health care organization leaders have
taken to mitigate this problem in the past and present and how they plan to continue in the future.
The findings of this study could assist health care organizations with the efficient management of
health information technology, thereby resulting in quality care delivery leading to a good
business reputation.

84
Role of the Researcher
The role of the researcher was to research to find out management issues associated with
health information technology. This was done by undertaking some data collected through
literature reviews, interviews, listening to what is being said, thinking, and analyzing themes
derived to formulate data. Other emerging methods that could be used as described by Yates and
Leggett (2016) included the innovative data collection.
According to Yin (2018), there are inherent concerns that the researcher, using qualitative
methods, must mitigate personal bias to the best of their ability. As the measurement instrument,
a qualitative researcher will interpret data sources based on their worldviews shaped by their
previous events and experiences. I used philosophical worldview as the foundation on which
they build their research methodology. Creswell and Poth (2018) stated that researcher bias is a
primary methodological concern in qualitative studies. In this study, they were not biased
implications because the researcher is not in the healthcare provider field.
To mitigate this issue, the researcher needs to apply the concept of bracketing as
suggested by Dodgson (2017). This means that the researcher must disengage his or her feelings,
experiences, and knowledge when interacting with the study participants (Dodgson, 2017). The
researcher acknowledges anything about themselves that could have any bearing on their
relationship with the study participants or the context in which they conducted the study and any
actions they took to minimize bias. Ahern (1999) stated that bracketing demonstrates the validity
of data collections and the analytical process.
Summary
The researcher must set aside personal biases during the research process (Creswell &
Poth, 2018); since personal experiences and influence could contaminate the sanctity of the data

85
being collected. In other words, the researcher must mitigate biases, assumptions, and
expectations of what he or she feels are the factors contributing to management issues with
health information technology. Otherwise, all these factors could negatively influence the data
collection and the analysis, leading to wrong or biased conclusions and recommendations
(Creswell & Poth, 2018).
Research Methodology
The purpose of this section of the paper was to provide and discuss the methodology that
will be used to conduct a study on current management issues in the health information
technology as relates to patient safety related to medical errors resulting in a negative impact on
the firm’s business reputation. The method for this study was qualitative analysis. Data
collection was derived from the review of literature from case studies dealing with the subject
matter. Themes derived from the literature review based on the problem statement, research
questions and interviews were used to formulate the data.
Discussion of the Flexible Design Method
Qualitative case design refers to studying a case with the bounds of a real-life
contemporary context or setting (Yin, 2018); however, not with a methodology but with what
must be studied (Stake, 1995). Stake (1995) stated that the identification of a specific case is
bounded by parameters such as place and time. The intent may be intrinsic or instrumental with
the goal of presenting an in-depth understanding of the case. Data analysis is a feature of case
study design which involves the study of single or multiple cases in which a description of the
case is provided along with the themes and issues or specific situations. The way the data are
presented may be chronological across cases or theoretical. The structure depends on the
research problem and case itself. Yin (2018) described case study research design as an

86
investigation of one or more specific instances of something that comprises cases in the study.
Yin (2018) stated that a case can be something more concrete like an organization, an individual,
or a group, or something more abstract as an event, a management decision or program. Yin
(2018) also defined some common features for case study as including the following features: In
depth study of several smaller cases studied in real life context and the use of multiple sources of
data including interview, observation, archival documents, and physical artifacts.
The case study method was more appropriate for the researcher’s chosen research study
because it sought to address a problem within the business environment which dealt with the
inefficient management of health information technology. As discussed above, the case study
design addresses descriptive questions. A case study research design encompasses an
investigation of one or more specific instances and something more concrete like an
organization, individual and a group or something more abstract like a management decision
(Yin, 2018). Hence case study research of an organization such as Lancaster General Hospital on
the mismanagement of health information technology was suitable.
Discussion of the Flexible Qualitative Method
This study was conducted with a flexible design using qualitative methodology,
specifically a single case study design was used. This type of design allowed the researcher to
gain more contextual and an in-depth knowledge about the specifics of management issues in
health care information technology management within Lancaster General Hospital in Lancaster,
Pennsylvania. The qualitative research design method is an appropriate approach for seeking the
solution to the research problem stated through the research questions as well as the employment
of the case study method; since the desire of the researcher in this study sought the understanding
of specific issues that are causing the mismanagement of health information technology with

87
regards to patient safety issues in medical errors and harm leading to the negative business
reputation of the organization. González Macias and Cuevas Contreras (2019) stated that
qualitative research seeks to explore reality just as others may experiment with it through the
interpretation of their beliefs, feelings, and values. Because of that, it follows a path towards
flexible and holistic investigation about persons, organizations or groups that are objects or
phenomenon. Thus, leading to the quality and complexity which are the essence of what is being
studied.
Applicable to the research question inquiring how the mismanagement of health
information technology within health care organizations has led to the disruption of quality care
delivery resulting in medical errors and negatively impacting the firm’s business reputation.
According to Hamilton and Finley (2019), qualitative research methods are the essential
component of implementation research. Which means that they are the study methods which use
strategies to adopt and integrate evidence-based health intervention into clinical and community
environments to improve health outcomes.
Discussion of the Triangulation Method
Triangulation involves using multiple data sources to corroborate the same findings.
There are four types of triangulation methods: Data triangulation, investigative triangulation,
theory triangulation, and method triangulation (Yin, 2018). According to Noble and Heale
(2019), data triangulation includes periods, space, and people. Investigative triangulation consists
of the use of several researchers in the study. Theory triangulation promotes the use of several
theoretical methods to interpret a phenomenon. Finally, methodological triangulation encourages
the use of several data collection methods such as interviews and observations. In this study,
methodological triangulation promoted interviews and observations as other sources that could

88
enhance data credibility in a qualitative case study. Hence, it was the appropriate triangulation
method to use. In this study, the researcher used in-depth recorded semi-structured telephone
interviews with a sample of healthcare providers and other healthcare professionals within
Lancaster General Hospital (LGH).
Participants
The participants eligible for this study included a team of healthcare professionals at
Lancaster General Hospital. They were medical doctors, Doctor of Nursing practitioners, nursing
practitioners, clinical informatics in nursing administration, managers of health informatics, and
informatics specialists working in various medical divisions within Lancaster General Hospital
and E-health operations. Other participants included the director of quality improvement within
Epic solutions and clinical applications, the director of health information management and
entity privacy officer, managers of risk department, the executive director of ACO inter-
community care, the pharmacist, and the regional director of operations. The researcher selected
this health care organization because it demonstrates the best practices of care through its
adoption and implementation of health information technology. Lancaster General Hospital has
emerged as one of the leading healthcare organizations in technological innovation. In 2021, the
hospital was awarded the prestigious College of Healthcare Information Management Executives
(CHIME) Digital Health Most Wired recognition. This great honor was granted to the hospital,
accrediting it at an impressive, certified level 8 in both the acute and ambulatory categories
(lancastergeneralhealth.org).
Population and Sampling
This section first discussed the population by describing the characteristics of the eligible
participants, why they were appropriate for this study, and the size of the eligible population.

89
Second, the sampling method and its appropriateness, the sample frame, and why it was
appropriate. Third, the desired sample and size, their appropriateness, and how the sample size
helped the researcher reach the saturation point. Additionally, a discussion of how the researcher
gained access to the sample.
Discussion of the Population
Rahi (2017) described the population as all people or items one wishes to understand.
According to Asiamah et al. (2017), a population is a group of individuals who have one or more
characteristics of interest. In this study, the potential population was comprised of Medical
Doctors (MD), Doctor of Nursing Practitioners (DNP), Nursing Practitioners (NP), clinical
informatics in nursing administration, managers of health informatics, and informatics specialists
working in various medical divisions within Lancaster General Hospital and E-health operations.
This team of professionals demonstrates characteristics that their organization describes as “the
dedicated and exceptional Lancaster health care staff.” It comprises serving neighbors,
employees, and other stakeholders as respectful, expert, and caring partners in their health,
through the creation of innovative, effective, and affordable systems
(lancastergeneralhealth.org).
According to Ellis (2021), case study research may include one or more individuals who
have been studied over time. Data saturation ensures that the researcher obtains adequate data to
answer the research questions. It occurs when additional information no longer changes the
researcher’s understanding of the concept under investigation (Tran et al., 2017). In this study,
the researcher conducted detailed data collections to obtain detailed information that sufficiently
answers the research questions for this study. Hence, the sample size is influenced by the
saturation point. The eligible participants are appropriate for this study because they are subject

90
matter experts and the continue to explore and develop solutions to address the current
challenges and future opportunities in health and information technology
(lancastergeneralhealth.org).
Discussion of Sampling
Sampling is a process of selecting part of the population for investigating to measure
characteristics, beliefs, and attitudes of a population (Rahi, 2017). According to Farrugia (2019),
sampling is guided by research questions and the conceptual framework in qualitative research.
Sampling can be classified into two major categories: conceptually driven and non-conceptually
driven (Farrugia, 2019). In this study, the researcher used a conceptually driven approach known
as a purposive sample. This type of sampling involves the researcher purposefully selecting a
model they believe would be the most beneficial in answering the research questions (Farrugia,
2019). Non-conceptually driven approaches have no particular emphasis in their sampling
approach and are more applicable to complex and multiple cases (Farrugia, 2019). Since this
study uses a single case study, a non- conceptually driven system will not be applicable.
According to Vasileiou et al. (2018), purposive sampling provides factual information relevant to
the study under investigation. This type of sampling is appropriate because it allows the
researchers to collect data from suitable participants with specific knowledge, experiences, and
direct involvement in the subject matter (Vasileiou et al., 2018).
Discussion of Sampling Frame
Asiamah et al. (2017) stated that since the researcher focuses on participants who can
offer the best experiences and thoughts to address the research goal in a qualitative inquiry, it is
necessary to specify the target population. In this study, the target population included team
members of healthcare professionals who utilize various forms of health information technology

91
for care delivery. The qualitative case study research information is collected through interviews,
observations, and assessing other sources such as written or electronic records (Creswell & Poth,
2018). Farrugia (2019) concurred that researchers may analyze documentary evidence such as
photographs, online forums, and web pages.
Discussion of Sample and Sample Size
Hamilton and Finley (2019) stated that individual qualitative interviews focus on talking
to key stakeholders, commonly referred to as multilevel stakeholders, because they can offer
valuable information to the research questions. This study's sample included healthcare workers
with knowledge, capabilities, and experiences with health information technology. These
participants were a team of professionals at Lancaster General Hospital, specifically Medical
Doctors (MD), Doctor of Nursing Practitioners (DNP), Nursing Practitioners (NP), clinical
informatics in nursing administration, managers of health informatics, and informatics
specialists. Other participants included the director of quality improvement within Epic Solutions
and clinical applications, the director of health information management and entity privacy
officer, managers of the risk department, the executive director of ACO inter-community care,
the pharmacist, and the regional director of operations. According to Sim et al. (2018), the
sample size depends on the scope of the research questions, and the more specific the
characteristics of the participants, the smaller relative to the study's goal, the smaller the sample
size. Since interviews for this study were conducted with a team of participants at Lancaster
General Hospital with specific characteristics, the sample size was medium to small. It consisted
of twenty participants. Generally, sample sizes in qualitative research are smaller to support the
depth of case study-oriented analysis critical for this type of inquiry (Vasileiou et al., 2018).

92
Saturation is reaching no new data, new themes, or codes, which signifies the fulfillment
of qualitative rigor (Vasileiou et al., 2018). Overall, it refers to the point when data collection
issues begin to be repetitive and thus result in redundant data collection (Hennink et al., 2019).
While saturation is used to determine sample sizes in qualitative research, Hennink et al. (2019)
argued that more guidance still needs to be on what influences saturation. Therefore, one of the
methods that the researcher applied was snowball sampling. According to Farrugia (2019), this
method involves asking the identified participants to recommend other possible participants for
the study. The researcher used this method to reach the saturation point. In this study, when the
participant's responses to the interviews looked similar after interviewing numerous participants,
the researcher realized that they had reached the saturation point; however, continued interviews
to the maximum of 21 participants.
According to Devers and Frankel (2000), gaining access to the sample can be done in
many ways, including securing permits from the gatekeepers. In this study, the researcher first
wrote a letter to the director of Lancaster General Hospital requesting permission to conduct
telephone interviews with the participants. Upon approval, the Lancaster General Hospital
director of health information technology was assigned to the researcher as the main point of
contact to help identify and provide the potential candidates' names and professional titles.
Before they could do that, the researcher had to submit a request to the Lancaster General
Hospital IRB. Upon acceptance of the letter by the IRB, the researcher then submitted the
protocol form, consent letter, and participant invitation letter to IRB to gain approval for the
primary contact to resume the recruitment of the potential participants via email and forward
them to the researcher. After Lancaster General Hospital IRB had conducted and evaluated the
proposed project, approval was granted to the researcher, and a copy was sent to the main contact

93
to start the recruitment using purposive sampling. This type of sampling involves the researcher
purposefully selecting a model they believe would be the most beneficial in answering the
research questions (Creswell & Poth, 2018). According to Creswell and Poth (2018), when
conducting a study, a researcher protects the anonymity of the participants by assigning numbers
or aliases to individuals. In this study, the researcher applied a coding system using codes labeled
P1 to P21 to protect participants' privacy and maintain confidentiality.
Data Collection and Organization
This section will first provide an overview of the data the researcher planned to collect
and how they managed it, and state why the chosen plan was appropriate for this research
project, while discussing the inclusion of member checking and follow-up interviews. Second,
the researcher will discuss the instruments that they applied, including a semi-structured
interviews interview guide used and archival data gathered and state how these two instruments
address the research questions and include a copy of the interview guide in the appendix. Third,
provide an overview of how they planned to organize data gathered in the research and why it is
appropriate. Finally, the researcher will conclude this section with a summary of the data
collection and organization.
Data Collection Plan
The data the researcher planned to collect dealt with potential management issues
associated with health information technology. Creswell and Poth (2018) noted that before a
researcher starts to collect data, it is important to seek permission from the Institutional Review
Board (IRB) because this provides evidence that the study is compliant with ethical research.
The researcher first started by seeking permission to do so. Then, upon approval by the IRB,
based on the researcher’s research design, she followed the data collection activities described by

94
Creswell and Poth (2018). They consisted of locating a site or individual, gaining access, making
rapport, sampling purposefully, collecting information, recording, exploring field issues, and
storing data. According to Yin (2018), the case study method includes general rules and
procedures for a researcher to collect data, hence, those as mentioned above were appropriate for
this study. Yin (2018) described some standard features of case study research as including the
use of multiple sources of data such as archival documents. Observations, artifacts, and
interviews. In this study, the primary sources of data collection included semi-structured
interviews, organizational documents, and records. As stated by Creswell and Poth (2018), all
these activities will be conducted, including having institutional approval and following the
consent, recording, and storage protocols.
When conducting interviews in qualitative research, it is essential to conduct member
checking to ascertain the trustworthiness of the results (Birt et al., 2016). Member checking is a
method of returning an interview or data to be analyzed. To enhance the reliability and validity
of the data the researcher gathered, recognizing, and respecting the LGH participants’ busy
schedules, the researcher conducted member checking during the interviews by restating and
summarizing information and then questioning the participant to determine the accuracy. Follow-
up interviews enable the researcher to investigate the study from multiple angles. Follow-up
questions are helpful to a researcher because they provide a safe approach (Roberts, 2020).
Several participants expressed a sense of empowerment during the initial interview when they
shared their narratives with a receptive audience, as opposed to the member-checking interview,
where they perceived the researchers to have more influence over the interpretations of their
statements (Motulsky, 2021).

95
Instruments
As the researcher previously noted, Yin (2018) stated that the case study method
comprises general rules and procedures to follow in the data collection process. In this study, the
researcher used semi-structured interviews and archival data to collect data. According to
Creswell and Poth (2018), a qualitative interview guide consists of the interviewer and
interviewee, the time, place, the interviewee's position, a brief description of the project, and
interview questions. Its structure varies depending on the method used to conduct it. For
instance, with a face-to-face interview, both the interviewer and interviewee are physically
present in the same room, whereas telephone interviews or other technologies are not (Creswell
& Poth, 2018). The researcher used the telephone to conduct semi-structured interviews and
included the interview protocols noted above in this study. Cachia and Millward (2011) stated
that telephone interviews provide more flexibility than face-to-face ones in setting up a
convenient place and time for the interviewer and interviewee. A telephone interview offers
control over privacy, is more cost-effective, and allows quicker participant access (Cachia &
Millward, 2011). Whiting (2008) stated that other components include an audio recording in
collecting data because it allows for permanent interview recording and frees the interviewer
from manual notetaking. The researcher incorporated this in the interview guide.
The interview questions outlined in Appendix A address the research questions as
follows: The first interview question addressed the first research question as it sought to
understand the potential management issues associated with health information technology
resulting in medical errors. The second interview question addressed the third research question
inquiring how the mismanagement of health information technology has led to the disruption of
quality care delivery resulting in a negative impact on the organization. The third interview

96
question addressed the second research question that sought to understand why the potential
management issues in health information technology occur. The fourth interview question
supported all three research questions by inquiring about what strategies are in place to ensure
the efficient management of health information technology. The last interview question solicited
further information about the subject matter not included in the other four interview questions.
According to Bearman (2019), asking an interviewee if there is anything else they would like to
add at the end of the interview allows them to provide open-ended comments on the subject
matter, resulting in the enrichment of data.
Das et al. (2018) described archival data as data gathered and stored for an intended use
later. It has many forms or records and, among others, history. According to Creswell and Poth
(2018), organizational archival data includes annual reports, policies, procedures, and the like.
As Yin (2018) noted, most corporate documentation is available through Internet searches,
including formal studies or evaluations that are useful for research, which consist of new
clippings and articles on company websites. In this study, the researcher reviewed organizational
documents available with the permission of Lancaster General Hospital's health information
director.
The researcher reviewed the organization's news articles on the website and other
relevant studies related to how Lancaster General Hospital adopted, implemented, and used
health information technology. Yin (2018) stated that reviewing organizational documents is
helpful in corroborating and augmenting evidence from other sources, hence, reviewing the
archival data helped gather important information surrounding the potential management issues
with health information technology and thereby apply the findings to address the research
questions in this study.

97
Data Organization Plan
Creswell and Poth (2018) noted that the process of analyzing data first begins with
organizing data collected. Data organization involves reading through the database, coding, and
interpreting the themes. Data organization depends on the approach used to collect data. There
are several methods which include the following: developing backup files; using audio
recordings for recording interviews; creating a master list for the information collected and
protecting participants with anonymity.
In this study, the researcher employed the following data organizational plan. First, she or
he used an interview transcript for the data collected from the semi-structured interviews. In this
process, they transcribed the interview questions and responses verbatim into a word document.
The researcher evaluated, cross-checked the responses, and then saved them to a flash drive and
derived themes and coded them according to commonality. One other method the researcher
applied was NVivo software. According to Alam (2020), this software is used for coding and
analyzing data. Foremost, it reduces the manual process by applying data management tools. The
researcher also coded the archival data with labels based on the themes, stored all the written
organizational documentation in file cabinets, and created a spreadsheet on each cabinet's
composition. Then, using the flash drives, they saved the electronic data, labeled it, and stored it
in the file cabinet, which will stay locked for security and privacy. Lastly, the researcher added
encryption to any electronic data through email and created a password with saved company
searched websites for the researcher’s laptop.
Summary of Data Collection and Conclusion
Data collection and organization involve drawing up a data collection plan, data
collection instruments to be used in the study, and how the researcher will collect and organize

98
data (Creswell & Poth, 2018). In this study, the data collection plan first sought permission and
gained approval from the IRB. It is then followed by locating the site, gaining rapport, sampling,
collecting data, organizing, and storing it (Creswell & Poth, 2018). The instruments that the
researcher used in this study were semi-structured interviews and archival data. The researcher
followed the interview guide in Appendix A to conduct the interviews. Next, the researcher
collected the archival data by reviewing written organizational documents like annual reports,
records, procedures, and the like.
The researcher reviewed any other related electronic news and information on the
company website. In organizing the collected data for this study, they included the interview
transcript, which the researcher transcribed verbatim into the Word document and coded it. They
used NVivo to perform data coding electronically as it reduced the manual data management
process. Finally, the researcher organized data gathered from organizational documentation with
labels and codes and stored it in locked file cabinets. They created a password and encryption for
email data to protect any information saved on the researcher’s laptop. Upon completing the data
collection and organization, the researcher was then able to proceed with the discussion of how
she or he will conduct the data analysis.
Data Analysis
In this section, the researcher first discusses the process for reading and memoing
emergent ideas, followed by the discussion of describing and classifying codes into themes. And
then the discussion of developing and accessing interpretation. Lastly, the researcher discusses
triangulation analysis, providing a detailed discussion of how she or he planned to analyze the
interview data, specifically a discussion of triangulation with quantitative and qualitative analysis
methods.

99
Emergent Ideas
Creswell and Poth (2018) stated that reading and memoing emergent ideas follow after
completing data organization. To begin the analysis of data involves reading the document
containing the data as many times as possible to make sense of it (Creswell & Poth, 2018).
According to Alam (2020), reading and revising the interview transcript leads to clustering
contents into codes mad, highlighting frequent words used to gain evidence for the research
question. Memoing involves writing notes on themes in the margins of the transcripts, field
notes, or images to explore a database further. It is also a means of sketching reflective things
and summarizing notes (Creswell & Poth, 2018). According to Finfgeld-Connett (2014),
reflective memos are letters about the data outlined during the data analysis. Coded data are
organized, classified, integrated, and interpreted during this process.
Coding Themes
The process of describing themes deals with the researcher providing information they
see with the content of the setting of a phenomenon they are studying (Creswell & Poth, 2018).
When using this process, coding becomes the center of qualitative research as it provides the
meaning of the information collected from interviews, documentation, and other observations
(Creswell & Poth, 2018). According to Creswell and Poth (2018), the coding process deals with
combining the written and visual data into miniature categories of information to find evidence
for the codes from various databases used in the study. Classifying involves sorting qualitative
data into categories and themes. It consists of finding five to seven general themes or types
(Creswell & Poth, 2018). According to DeCuir-Gunby et al. (2011), codes are labels used for
assigning descriptive information finalized in a study. Meaningful labels are assigned extensive
data with phrases or sentences connected with a specific setting or phenomenon.

100
Interpretation
According to Creswell and Poth (2018), the interpretation of data begins with developing
themes and codes to make an analytical conclusion to the data presented and goes further into the
greater meaning of the data. Realizing the bigger picture occurs during the first three steps:
compiling, disassembling, and reassembling (Castleberry & Nolen, 2018). After reassembling
data through coding, the researcher can derive excerpts and make sense of them with others
(Castleberry & Nolen, 2018). Doing so allows the researcher to interpret what happens within
various experiences, histories, and the like. Thereby begin to identify thematic patterns within
the data. These themes present the concept's importance under investigation concerning the
research question (Castleberry & Nolen, 2018).
Data Representation
Castleberry and Nolen (2018) stated that a visual representation of themes, codes, and
their relationship happens through the development of maps. These maps contain detailed
information on the description of themes, patterns identified, and coded data. Creswell and Poth
(2018) stated that this process represents data packaged in text, tabular, or figure form.
Qualitative data software such as NVivo helps develop data visualizations (Castleberry & Nolen,
2018). The data visualization appears in a three-dimensional map of code clusters. Reviewing
data allows the researcher to see the relationship between constructs that are not evident
(Castleberry & Nolen, 2018).
Yin (2018) noted that triangulation helps the researcher collect and analyze data from
multiple sources to corroborate the same evidence and helps strengthen the validity of the case
study. There are four types of triangulations: data, investigator, theory, and methodological. In
analyzing the interview triangulation, it is essential to ensure that the participants' perspective in

101
the study is accurate (Yin, 2018). In this study, the researcher used methodological triangulation
to conduct the analysis of the interviews. Jaspers (2009) stated that methods triangulation
comprises various data collection and analysis methods. This involves combining approaches
from the qualitative and quantitative research methods. To conduct triangulation analysis in this
study using telephone interviews, the researcher employed the software NVivo which, according
to Creswell and Poth (2018), is used for qualitative analysis of video, audio, and still images
analysis. The researcher also used archival data and a literature review to triangulate. For
triangulation using the quantitative approach, the researcher incorporated descriptive statistical
packages such as Statistical Package for the Social Science (SPSS).
Summary of Data Analysis
The process of analyzing data involves the following steps: reading and memoing
emergent ideas; describing and classifying codes into themes; developing and accessing
interpretations and finally, conducting triangulation analysis (Yin, 2018). Reading the document
containing data is the first step in the analysis. It entails reading data several times to ascertain its
meaning. This process works in conjunction with memoing, whereby the researcher writes notes
in the margins of a transcript and other documents with data. Once this process is complete, the
description of themes is information seen in the content setting of the concept provided. Then
they are coded and classified into qualitative categories and themes. Interpreting the data starts
with developing themes and codes into analytical conclusions. This process provides the
formulation to analyze the concept under investigation. Next is the process of data visualization,
which represents themes, codes, and their relationship through maps. Software packages like
NVivo are used for producing visualization. Finally, the data analysis process concludes with the

102
triangulation analysis for this study's interview data, which applies both quantitative and
qualitative approaches, a methodological triangulation.
Reliability and Validity
This section discusses how the researcher ensured reliability by applying credibility,
transferability, dependability, and confirmability. Second, they discussed how they provided the
study's validity with bracketing, triangulation, and saturation. Lastly, it discusses the bracketing
technique that the researcher employed to address biases such as those in the anticipated themes.
A qualitative study has multiple ways of addressing reliability and validity (Creswell & Poth,
2018).
Reliability
According to Yin (2018), reliability demonstrates that data collection procedures are
repeated in a given research study and continue to produce the same results. Creswell and Poth
(2018) stated that to establish the trustworthiness of an investigation, researchers use methods
such as credibility, transferability, dependability, and confirmability. Credibility refers to the
confidence placed on research findings by establishing whether they were credible information
from the participants' original data (Korstjens & Moser, 2018). It is rooted in actual value, which
seeks to understand whether the researcher developed and interpreted the findings based on the
concept or phenomenon under investigation (Lemon & Hayes, 2020). Transferability refers to
how the researcher could apply qualitative research results to other settings or contexts (Lemon
& Hayes, 2020). Dependability refers to the stability of the findings over time (Korstjens &
Moser, 2018).
Dependability shows that research findings are exclusive to a specific time and place,
with data having consistent explanations (Lemon & Hayes, 2020). Lastly, confirmability

103
involves the degree to which other researchers could confirm the researcher's findings on the
study, and it also establishes the results derived from the data. In this study, the researcher first
employed credibility because it values truth and has enabled the researcher to use various
methods, such as member checking and triangulation, to ascertain the reliability of data
(Creswell & Poth, 2018). Next, she or he employed both dependability and confirmability, which
according to Korstjens and Moser (2018), constitute an audit trail as they describe the research
process from the beginning of the study to the development and interpretations of the findings.
Finally, the researcher employed the transferability approach, which would allow the readers
using health information technology to assess if the results of this research project apply to their
settings.
Validity
Creswell and Poth (2018) described validity in qualitative research as a method of
assessing the accuracy of the findings. There are multiple ways of validating data. They are
classified into the following strategic categories: researcher's lens, participants' lens, and readers'
or reviewers' lens (Creswell & Poth, 2018). The researcher's lens involves the researcher
checking the accuracy of the results through triangulation, clarifying bias, and discovering
disconfirming evidence. Participants' lens involves member checking, lengthy engagements,
observations, and collaboration with participants. Finally, the readers' lens includes enabling
external audits, generating detailed descriptions, and having peer-reviewed data (Creswell &
Poth, 2018). To ensure validity in this study, the researcher employed the researchers' lens and
the member-checking aspect of the participants' lens.

104
Bracketing
To further strengthen the assurance of the validity of this study, the researcher employed
the following approaches: Bracketing and saturation. Bracketing involves the researcher
disregarding their feelings, experiences, and knowledge when interacting with participants
(Dodgson, 2017). It consists in acknowledging anything about themselves that could have any
bearing on the relationship with the study participants or the context in which the study was
conducted and any actions to minimize bias (Dodgson, 2017). According to Ahern (1999),
bracketing demonstrates the data collection and analysis process's validity. Hence, the researcher
will employ it to validate the findings.
Triangulation
Triangulation involves using multiple data sources to corroborate the same findings.
There are four types of triangulation methods: Data triangulation, investigative triangulation,
theory triangulation, and method triangulation (Yin, 2018). Noble and Heale (2019) stated that
data triangulation includes periods, space, and people. Investigative triangulation consists of the
use of several researchers in the study. Theory triangulation promotes the use of several
theoretical methods to interpret a phenomenon. Finally, methodological triangulation encourages
the use of several data collection methods, such as interviews and observations. In this study, the
researcher used methodological triangulation by applying interviews, observations, and archival
data to enhance data credibility in a qualitative case study. According to Lemon and Hayes
(2020), triangulation is a qualitative research technique used to test validation by exchanging
information from different sources having dissimilar data and independent sources for
corroboration of the subject matter under investigation.

105
Saturation
Saturation is reaching no new data, new themes, or codes, which signifies the fulfillment
of qualitative rigor (Vasileiou et al., 2018). Overall, it refers to the point when data collection
issues begin to be repetitive and thus result in redundant data collection (Hennink et al., 2019).
Morse (2014) stated that data saturation occurs when a researcher determines that the supply of
additional data will provide minute information on the study under investigation and, therefore,
reflect the data's validity. In this study, the researcher applied data saturation by facilitating
adequate data collection, which provides information related to the research question and
supports the research.
Bracketing Techniques
Bracketing is an approach conducted to separate the researcher's biases and assumptions
from their own experiences, feelings, and knowledge to ascertain a complete understanding of a
phenomenon received by participants in a study (Cypress, 2017). The researcher's biases are
influenced by approaches such as reflexivity, whereby they engage in their own biases and
prepositions that apply to the study (Cypress, 2017). Bracketing is a process that researchers use
to make checks and balances to counteract biases (Fischer, 2009). It involves the researcher's
recognition of anticipated interests, personal experiences, and other factors that can influence
how they view data in the study (Fischer, 2009). One technique Fischer (2009) suggested
employing to address this is the process of engagement, whereby participants are engaged in
elaborating their descriptions. Doing so allows for revisiting their earlier understanding of the
data and providing a more in-depth one. In this study, the researcher employed reflexive and
engagement approaches to address biases in their anticipated themes. Reflexivity allowed the
researcher to monitor and control his or her self-awareness and view the study more objectively.

106
Engaging the participants helped catch any reassumptions the researcher may have had at the
initial data collection and provided in-depth data to enhance credibility.
Summary of Reliability and Validity
The process of reliability in qualitative research is used to ascertain the trustworthiness of
the study under investigation through techniques such as credibility, transferability,
dependability, and confirmability. In this research, the researcher applied all four techniques.
Credibility enabled the researcher to use various methods, such as triangulation and member
checking. Dependability and confirmability assisted with describing the research process from
the beginning to the interpretation of the findings. Transferability allowed other readers to use
the concept under investigation to assess if the results it yields apply to their context. Validity in
qualitative research is used to evaluate the accuracy of the findings through multiple techniques
such as triangulation, bracketing, and saturation. In this study, the researcher employed
methodological triangulation to enhance data credibility, as it allows for data analysis and
interpretation to be drawn from multiple sources (Yin, 2018). The sources included interviews,
observations, and archival data. Second, she or he used the saturation method because it
facilitated adequate data collection for the study under investigation. Finally, applied bracketing
in validating data collected assisted in setting the researcher's biases and assumptions that can
affect the validity of the data.
Summary of Section 2
This study aimed to explore and understand potential management issues surrounding
health information technology within the health care industry resulting in the disruption to the
provision of quality care that negatively impacts business reputation. Section 2 provided the
following components for the study: The purpose statement, the role of the researcher,

107
methodology, participants, population and sampling, data collection and organization, data
analysis, and reliability and validity of the data. The purpose statement stated why the study was
conducted and how its findings would impact the efficient way health care organizations use
health information technology, that would lead to a positive business reputation. The role of the
researcher discussed actions that a researcher will take in conducting the study, including the
employment of bracketing techniques to avoid personal bias and assumptions as they may
negatively influence data collection and analysis, thereby lead to wrong conclusions. The
research methodology provided a discussion of the single case design, flexible qualitative
method, and methodological triangulation used and their appropriateness for this study. The
participants' section described the type of individuals eligible for the research and the
justification of why they are eligible. Population and sampling described the characteristics of
the eligible participants, the size, and appropriateness for this study. The sampling discussion
included the sampling method, sampling frame, size, and suitability to this research study.
Data collection and organization provided an overview of what data are to be collected,
how it will be collected, and its appropriateness to this research. It incorporated member
checking, follow-up interviews, instruments to collect data and how the researcher will organize
it, and the justification of why the plan is appropriate for this study. Data analysis provided how
the researcher will organize data and analyze it with the inclusion of emergent ideas, themes
coding, interpretation, data representation, and analysis for triangulation. Reliability and validity
provided a discussion of how the researcher will ensure the trustworthiness of the findings. With
reliability, the discussion included credibility, transferability, dependability, and confirmability.
The researcher discussed how to confirm validity using bracketing, triangulation, and saturation.

108
This section concluded with the discussion of bracketing techniques that the researcher will
employ to address any biases such as anticipated themes.
Conclusion
The purpose of this qualitative case study was to identify and discuss issues surrounding
the inefficient management of health information technology as they affect the delivery of
quality health care, resulting in a negative impact on the organization's business reputation. To
realize the objective of this study, the researcher formulated the research into Section 1, focusing
on the foundation of the study and Section 2 as the project.
Section 1 provided the following key components for the study: introduction to the study,
the background of the problem, the problem statement, the purpose statement, research
questions, nature of the study, conceptual framework, the definition of terms, assumptions,
limitations, delimitations, the significance of the study, reduction of gaps in the literature, the
implication to biblical perspective and benefits to business practice and relationship to cognate.
The background of the problem and problem statement discussed benefits associated with the
efficient use of health information technology and the management issues that can result in
problematic outcomes. The research questions provided sought to find answers to the problems
associated with the subject matter. The nature of the study described the methodology that would
be used to conduct the study. It included the discussion of the research paradigm, method, and
design.
The conceptual framework discussed the elements included in the research framework as
they relate to the problem statement. The definitions of terms and some of the frequently used
terms and acronyms in health information technology were provided. Assumptions, limitations,
and delimitations associated with the study were discussed. What makes this study significant

109
was discussed as it relates to the reduction of gaps in the literature, the implication of biblical
integration and benefits to business practice, and the relationship to cognate. The reduction of
gaps in the literature was provided to illustrate that there is still much open for the study in the
subject matter. The implication of biblical integration was discussed to demonstrate and
reinforce the significance of this business research as a means of advancing God's purpose for
business on earth. The benefit to business practice discussed that when used efficiently, health
information technology can result in business success.
Additionally, Section 1 provided a detailed review of the literature review outline on the
numerous benefits of health information technology to business practice. They included efficient
and effective health care delivery, productivity, cost reduction, research acceleration, proximity,
and many more. The literature also indicated that if not managed efficiently, health information
technology can result in some undesirable outcomes that can lead to the disruption of quality
care delivery and impact negatively impact the business. The literature review provided a
number of possible causes of the inefficient management of health information technology which
included issues with interoperability, lack of efficient design, development, adoption,
implementation, and usability. To address these issues, the literature also highlighted some
possible solutions which included training, user acceptance, leadership, and the like.
Section 2 provided the following components for the study: The purpose statement, the
role of the researcher, methodology, participants, population and sampling, data collection and
organization, data analysis, and reliability and validity of the data. The purpose statement stated
why the study is being conducted and how its findings would impact the efficient way health
care organizations use health information technology, that would lead to a positive business
reputation. The role of the researcher discussed actions that a researcher will take in conducting

110
the study, including the employment of bracketing techniques to avoid personal bias and
assumptions as they may negatively influence data collection and analysis, thereby lead to wrong
conclusions. The research methodology provided a discussion of the single case design, flexible
qualitative method, and methodological triangulation used and their appropriateness for this
study. The participants' section described the type of individuals eligible for the research and the
justification of why they are eligible. Population and sampling described the characteristics of
the eligible participants, the size, and appropriateness for this study. The sampling discussion
included the sampling method, sampling frame, size, and suitability to this research study.
Data collection and organization provided an overview of what data are to be collected,
how it will be collected, and its appropriateness to this research. It incorporated member
checking, follow-up interviews, instruments to collect data and how the researcher will organize
it, and the justification of why the plan is appropriate for this study. Data analysis provided how
the researcher will organize data and analyze it with the inclusion of emergent ideas, themes
coding, interpretation, data representation, and analysis for triangulation. Reliability and validity
provided a discussion of how the researcher will ensure the trustworthiness of the findings. With
reliability, the discussion included credibility, transferability, dependability, and confirmability.
The researcher discussed how to confirm validity using bracketing, triangulation, and saturation
and concluded with the discussion of bracketing techniques that the researcher will employ to
address any biases such as anticipated themes.
Transition to Summary of Section 2
The purpose of this qualitative case study was to identify and discuss issues surrounding
the inefficient management of health information technology as they affect the delivery of
quality health care, resulting in a negative impact on the organization's business reputation. To

111
realize the objective of this study, the researcher formulated the research into Section 1, focusing
on the foundation of the study and Section 2 as the project.
Section 1 provided the following key components for the study: introduction to the study,
the background of the problem, the problem statement, the purpose statement, research
questions, nature of the study, conceptual framework, the definition of terms, assumptions,
limitations, delimitations, the significance of the study, reduction of gaps in the literature, the
implication to biblical perspective and benefits to business practice and relationship to cognate.
The background of the problem and problem statement discussed benefits associated with the
efficient use of health information technology and the management issues that can result in
problematic outcomes. The research questions provided sought to find answers to the problems
associated with the subject matter. The nature of the study described the methodology that would
be used to conduct the study. It included the discussion of the research paradigm, method, and
design. The conceptual framework discussed the elements included in the research framework as
they relate to the problem statement. The definitions of terms and some of the frequently used
terms and acronyms in health information technology were provided. Assumptions, limitations,
and delimitations associated with the study were discussed. What makes this study significant
was discussed as it relates to the reduction of gaps in the literature, the implication of biblical
integration and benefits to business practice, and the relationship to cognate. The reduction of
gaps in the literature was provided to illustrate that there is still much open for the study in the
subject matter. The implication of biblical integration was discussed to demonstrate and
reinforce the significance of this business research as a means of advancing God's purpose for
business on earth. The benefit to business practice discussed that when used efficiently, health
information technology can result in business success. Additionally, Section 1 provided a

112
detailed review of the literature review outline on the numerous benefits of health information
technology to business practice. They included efficient and effective health care delivery,
productivity, cost reduction, research acceleration, proximity, and many more. However, the
literature also indicated that if not managed efficiently, health information technology can result
in some undesirable outcomes that can lead to the disruption of quality care delivery and impact
negatively impact the business. The literature review provided a number of possible causes of the
inefficient management of health information technology which included issues with
interoperability, lack of efficient design, development, adoption, implementation, and usability.
To address these issues, the literature also highlighted some possible solutions which included
training, user acceptance, leadership, and the like.
Section 2 provided the following components for the study: The purpose statement, the
role of the researcher, methodology, participants, population and sampling, data collection and
organization, data analysis, and reliability and validity of the data. The purpose statement stated
why the study is being conducted and how its findings would impact the efficient way health
care organizations use health information technology, that would lead to a positive business
reputation. The role of the researcher discussed actions that a researcher will take in conducting
the study, including the employment of bracketing techniques to avoid personal bias and
assumptions as they may negatively influence data collection and analysis, thereby lead to wrong
conclusions. The research methodology provided a discussion of the single case design, flexible
qualitative method, and methodological triangulation used and their appropriateness for this
study. The participants' section described the type of individuals eligible for the research and the
justification of why they are eligible. Population and sampling described the characteristics of
the eligible participants, the size, and appropriateness for this study. The sampling discussion

113
included the sampling method, sampling frame, size, and suitability to this research study. Data
collection and organization provided an overview of what data are to be collected, how it will be
collected, and its appropriateness to this research. It incorporated member checking, follow-up
interviews, instruments to collect data and how the researcher will organize it, and the
justification of why the plan is appropriate for this study. Data analysis provided how the
researcher will organize data and analyze it with the inclusion of emergent ideas, themes coding,
interpretation, data representation, and analysis for triangulation. Reliability and validity
provided a discussion of how the researcher will ensure the trustworthiness of the findings. With
reliability, the discussion included credibility, transferability, dependability, and confirmability.
The researcher discussed how to confirm validity using bracketing, triangulation, and saturation
and concluded with the discussion of bracketing techniques that the researcher will employ to
address any biases such as anticipated themes.
In Section 3, the researcher presented the findings of this research study, the supporting
materials, and their application to professional practice. The researcher provided an in-depth
narrative of the themes discovered and how they corroborate the potential problem being studied.
Based on the findings, the researcher recommended possible strategies that could be used for
improvement. The researcher stated the professional and personal the study reflected on her and
its biblical implications. They then concluded with some recommendations for further studies.

114
Section 3: Application to Professional Practice
Overview of the Study
This qualitative single case study aimed to identify and discuss current issues surrounding
the inefficient management of health information technology as they affect the delivery of
quality health care, negatively impacting the organization’s business reputation (Gauthier et al.,
2018). The study assesses steps the healthcare organization leaders have taken to mitigate this
problem in the past and present and how they plan to continue moving forward. The findings of
this study could assist healthcare organizations with efficiently managing health information
technology, resulting in quality care delivery and a good business reputation.
Presentation of the Findings
To resume the data collection, the researcher first wrote a letter to Lancaster General
Hospital Leadership requesting permission to gain access to the potential participants. Creswell
and Poth (2018) stated that before conducting data collection, the qualitative researcher must
seek institutional approval. Upon approval, the Lancaster General Hospital director of health
information technology was assigned to the researcher as the main point of contact to help
identify and provide the potential candidates' names and professional titles. However, before
they could do that, the researcher had to submit a request to the Lancaster General Hospital IRB.
Upon acceptance of the letter, the researcher then submitted the protocol form consent letter and
participant invitation letter to IRB to gain approval for the primary contact to resume the
recruitment of the potential participants via email and forward them to the researcher. After
Lancaster General Hospital, IRB had conducted and evaluated the project, approval was granted
to the researcher, and a copy was sent to the main contact to start the recruitment using purposive
sampling. This type of sampling involves the researcher purposefully selecting a model they

115
believe would be the most beneficial in answering the research questions (Creswell & Poth,
2018).
There was a total of 21 participants recruited from Lancaster General Hospital for this
study. They were medical doctors, Doctor of Nursing practitioners, nursing practitioners, clinical
informatics in nursing administration, managers of health informatics, informatics specialists and
registered nurses working in various medical divisions within Lancaster General Hospital and E-
health operations. Other participants included the director of quality improvement within Epic
solutions and clinical applications, the director of health information management and entity
privacy officer, managers of risk department, manager of clinical applications, manager of HIM
operations, manager of clinical coding, director of clinical operations, manager of clinical
quality, the executive director of ACO inter-community care, the pharmacist, and the regional
director of operations. According to Creswell and Poth (2018), when conducting a study, a
researcher protects the anonymity of the participants by assigning numbers or aliases to
individuals. In this study, the researcher applied a coding system using codes labeled P1 to P21
to protect participants' privacy and maintain confidentiality.
The researcher collected the research via telephone semi-structured interviews until the
data saturation point was reached. The interview questions are as shown in Appendix A. Upon
completion of data collection, the researcher then transcribed the data and applied it to NVivo
software (NVivo PRO12. n.d.) for analysis and categorization of data into themes derived. The
findings will be presented as follows:
1. State the themes discovered.
2. Discuss the interpretation of these themes.
3. Provide the representation and visualization of data.

116
4. Discuss in detail how the findings relate to the research question, conceptual framework,
anticipated themes, literature, and the problem.
Themes Discovered
As illustrated in Figure 2, the researcher organized the study findings into four themes
resulting from the interview results. First the researcher shows the research question, next the
theme that emerged then the components of the theme labelled code.
117
Figure 2
Four Themes from Interview Results
Table of themes discovered is illustrated below:
Theme 1. Users face a range of management challenges leading to inefficiencies.
Theme 2. A range of strategies used to ensure efficient management of HIT.
Theme 3. Management of issues lead to disruption in efficient delivery.
Theme 4. Users report more potential than actual impacts on reputation.
RQ1: Theme 1 How has the mismanagement of health
information technology within health care organizations led
to medical errors, disrupting health care delivery?
RQa: Theme 2 What Electronic Health Records management issues
contribute to medical errors?
Theme Theme
Code Code
Theme 1. Users face a range of management challenges leading to
inefficiencies
Theme 2. A range of strategies used to ensure efficient management of HIT
accuracy of user entries-coding audits by health information management team
communicating technology standards early adoption stakeholder analysis
documentation effective indexing of paper documents
federal policies-rules ensuring workflow efficiency
information access across systems frequent IT meetings
optimizing for the whole team huddling and project management
potential for provider error modified system to fit practice
privacy-security of health information policies and procedures
resistance to adoption smooth change control processes
software defects staff involvement and training
training to learn the system using best practice standards
transition from paper to electronic
updating of work queues
RQ3: Theme 4 How has the mismanagement of health
information technology within healthcare organizations led to
the disruption of quality healthcare delivery, resulting in
medical errors, and negatively impacting the organization's
business reputation?
RQ2: Theme 3 Why has the mismanagement of health information
technology negatively impacted patient safety and disrupted the
efficient delivery of health care?
Theme Theme
Code Code
Theme 4. Users report more potential than actual impacts on
reputation
Theme3: Management issues that lead to disruption in efficient delivery
no impact on business reputation backgrounds and training of senior leadership
potential impacts of disruption on business customization makes upgrades challenging
clinician complaints about system design design of tools
external organization ratings different style of practice
inaccurate information inefficiencies due to complexity of healthcare
information falling through cracks with updates lack of standards in data sharing
number of steps-amount of resources limits of product customization
system downtime prioritization of ticket to fix issue
time impact of documentation rules are confusing and constantly changing
waiting for updates-fixes
unannounced changes during updates
user inaccuracy

118
Interpretation of the Themes
Theme 1: Users face a range of management challenges leading to inefficiencies.
Many participants and references attributed the inefficiencies to training issues in
learning the system (P1, P2, P3, P11, and P19). These issues arose from products needing to be
centralized, end users not being well trained to use HIT efficiently, and learning being a bit
complicated initially but being able to catch on. Generally, most felt that training needed to be
adequate, and the learning curve was longer than it should be such that it caused things to fall
through the cracks. One other significant challenge stated was the transition from paper to
electronics. Participants felt that the change might have led to wrong coding on patients’ health
charts as most clinicians used the copy-and-paste feature to input data into electronic health
records. The transition also resulted in communication process delays. The next biggest
challenge was due to limited or lack of information across systems. Additionally, participants
mentioned other challenges, which included accuracy in user entries coding, communicating
technology standards, documentation, optimization for the whole team, potential provider error,
resistance to adoption, software defect, and privacy of health information.
P1 noted,
So um, I think the first issue that we had was um training, training, and staff competency,
and I'll go into some, for example, we had a lot with the old, filled record. There wasn't a
lot of higher education required because it was paper; we were managing paper, um, and
when we went to the EMR, of course, you had to learn a new skill and learn the
computer, and so we had some folks who really struggled with that but just were not
equipped for that. Um, that big of a change.

119
P1 stated that the first issue they encountered at the beginning of their transition from
managing paper to adopting electronic health records was due to training issues and staff
competency since the conversion required new skills and proficiency in using computers. It
resulted in some staff members facing challenges adapting to the new EMR technology they used
(P1). Learning how to operate and navigate the computer proved difficult, as well as
understanding the functionalities of the software and inputting data and retrieving it impeded
progress, thereby affecting efficiency. Realizing that training was a big challenge that needed to
be addressed to attain efficiencies, they started investing in training and equipping the staff with
the necessary competencies to ensure the efficient use of EMR (P1).
P2 noted,
I think one of so from my viewpoint from my vantage point I think one of the largest um,
some of them one of the largest I don't want to say issue but maybe challenges that an
organization case um is having, first of all, um well-staffed um in well trained I ki
department that understands the business needs of the end-users to be able to turn the turn
that into effective use of the HIT technology.
P2 echoed that one of the organization's significant challenges was having a well-trained
and staffed IT department that understands the users' needs to translate them for effective,
successful utilization. In today's world, health information technology is crucial for efficiently
managing healthcare services. Like P1, P2 stated that to overcome training challenges, the
organization must invest in comprehensive training and development programs for their staff.
P3 noted,
Helpful, but you got to do it trying to read an owner's manual for your new cell phone or
whatever, you know to understand how to use it until you do it process. So, in medical

120
practice, it's like changing the pilot in midair, you know, trying to take care of patients.
You know these people are sick, you're making very important decisions, and you learn a
new system where you can't do that efficiently and effectively uh without significant
slowing down.
P3 described the medical practice as very challenging since clinicians are entrusted with
the critical care of the sick and making important medical decisions about their well-being,
therefore are often under a lot of pressure. Given that, any change or disruption can affect their
efficiency. Introducing a new system like Electronic Medical Records (EMR) can be challenging
for medical practitioners to adapt fast due to the learning, time, effort, and other proficiencies
involved in efficiently using it. Given these challenges, P3 emphatically expressed similar beliefs
to P1 and P2, which called for organizations to carefully plan and manage the implementation
process by considering the timing and providing sufficient training and support with closely
monitoring the impact on patient care.
P1, P2, and P3 affirm that inadequate training in health information poses challenges in
the adoption and useability. Inadequate training on EHR impacted the clinicians’ ability to
communicate and coordinate efficient care and lack of trust was attributed to some inaccuracies
in the data entered, unclear notations and delayed data entry (Rathert et al., 2019). On the other
hand, for health care providers, these challenges are comprised of encountering difficulties in
protecting data and other issues related to the need to hire new staff, training, and organizational
restructuring (Gandarillas & Goswami, 2018).
Theme 2: A range of strategies used to ensure efficient management of HIT.
The participants discussed a wide range of strategies: audits, early adoption stakeholder
analysis, effective paper indexing, frequent IT meetings, huddling and project management, and

121
best practices. The strategy noted by most participants was that policies and procedures were put
in place to ensure efficiency. The major second strategy was staff involvement and training, as
stated in theme 1.
P7 noted,
I think we have very robust policies and procedures related to the use of healthcare
technology. I do think that there is... Here onboarding and ongoing education related to
the technologies that we use. For example, when there is an upgrade, education tip sheets
are made available ahead of time to those impacted by any change. I think we have great
knowledgeable resources on the technologies we use, such as the Epic medical record or
the 3M coder, or those types of those are the ones I'm used to using. So, I think those are
things that have contributed to the successes.
P7 spoke on how their organization takes pride in having robust policies and procedures
to govern the efficient use of health information technology. The organization's procedures for
implementing upgrades or changes to the system include proactive education and tip sheets in
advance for those to whom upcoming changes will impact. These allow staff to familiarize
themselves with new features and functionalities, thereby allowing them to be prepared and
equipped with the efficient use of the latest technology (P7). They support their staff with a
cultivated pool of knowledgeable resources who specialize in the technologies they use, such as
Epic EMR or 3m coder.
P8 noted,
So um, as my current role, um, I try to create standards, they're more local than national
or even regional standards across all of our data sharing partners. And so, for instance, we
work with Highmark and Aetna and um capital Blue cross and UPMC and you know, the

122
list goes on and on uh as payer partners and we have to share with them tons of data that
says whether we're doing a good job or a bad job from a quality care perspective, we run
into all those same issues that we, you know, previously just discussed. Um, and so what
we have done is we have created a standard way to share that data, and we tell players
this is how we can share it. If you can use this data, you can have it, but if you want
something custom, or probably not going to be able to do that for you. So, um, it sort of
shifts the work. It's not a great solution. It just puts more work on the payer to adapt their
systems to what we can provide. Um, but what we try to do is create standards when we
can uh because, you know, we don't have the workforce to have a different solution for
every organization that we have to share information with.
P8 described his current role as being responsible for establishing standards for data
sharing among various partners such as Highmark, Aetna, Blue Cross, UMPC, and others who
serve as their players. Since as part of their collaboration, there is a need to share a substantial
amount of data that reflects the quality of care they provide. In the process of doing so, P8
indicated that they often encounter challenges, so to address them, they have developed a
standard of data sharing that allows for the maintenance of consistent efficiencies in sharing the
necessary information. In conclusion, P8 stated that establishing standards for data sharing
among the payers is a crucial aspect of their work as it allows them to share quality care with
their partners effectively.
P7 and P8 support the strategy of using policies and procedures to ensure efficiency.
According to Alrahbi et al. (2021), among other motivators of efficient adoption of health
information technology by employees is the provision of speedy procedures, well-defined
procedures, and support for teaching hospitals and career development. Standards and

123
procedures are critical components of strategies needed for the successful adoption of HIT by the
stakeholders (Capurro et al., 2017).
Theme 3: Management of issues leads to disruption in the efficient delivery.
Most participants stated that the design of tools in HIT and inefficiencies due to the
complexity of healthcare were management issues that led to inefficiencies, resulting in the
disruption of quality care. Other areas of challenges included customization, different practice
styles, lack of standards in sharing data, and rules that constantly change and need to be clarified.
P9 noted,
Yeah. Um, part of it, um, is, in my opinion, in the design of the tools that clinicians use.
So, they're often just kind of cookie-cutter things that an analyst created somewhere and
may or may not help me render care for a patient with a specific condition. So, um, if
some of the documentation tools, for instance, were created to be uh more tuned, if you
will to the patient in front of me, I could probably document relevant information faster.
So, I get the benefits of both better documentation and improved efficiency. If the design
of the tools was improved.
P9 believed that the key contributing factors in health care documentation and
efficiencies are due to the design of tools used by clinicians. These tools are often standardized
in the nature created by the analyst without considering the specific needs of the clinicians
delivering care to the patients in various units. This lack of customization can hinder
documenting patient information efficiently. P9 suggested that clinicians could document
relevant information accurately when designing the tools if they were more attuned to each
patient's unique needs. As described by P 9, the improved tool design with templates and features

124
tailored to the specific condition or scenario would result in better documentation quality and
enhance efficiency in the documentation process.
P15 noted,
Yeah, and we're beginning to see more involvement of clinicians, midlevel practitioners'
physicians in uh design of those tools. Um, we're an expensive resource to sit in a
cubicle, not generate money. So those systems have been reluctant to have as much
clinical involvement in the design of the systems, um, as I think it would be helpful, but
you know, they're beginning to realize that that's an important piece of the puzzle. So, I
do. So, the last ten years have been transitioning to electronic records, and many health
systems are now saying, okay, we've converted. How do we get more value out of this?
So, they're starting to ask those questions about, uh you know, who should design the
tools, what should they do, how can they be made better? So, we're entering another 10-
year cycle of enhancement and optimization.
P15 echoed that there has been a growing need to involve clinicians, midlevel
practitioners, and physicians in the design of healthcare tools and systems. However, there was
some reluctance in the past due to the expenses that clinicians did not believe would generate
revenue. P15 further stated that in the past decade, as the transition from paper to electronics has
intensified, healthcare systems are asking essential questions about the design of tools, which
should be involved, what functionalities they should have, and how they can be enhanced to
serve clinicians and patients better. It is the belief that increased collaboration between
healthcare professionals and technology experts opens an opportunity for innovation and
improvement in healthcare systems as it allows for a more user-centered approach to create tools
that are intuitive, customizable, and effective in supporting the clinicians’ workforce (P15).

125
P6 noted,
Uh, there's a couple of reasons, um So I think one of the reasons is that you know we
have we still use different systems like the EHR has to talk to different systems including
like medication cabinets where medications are stored um and other things and so any
time that you're building these drug records in these systems that have to interface to
other systems it's just more complicated build that takes a lot more steps. The same thing
there's information that links into our I. V. Pumps, which is good like other things are
good, and you know when they're built and working right because they make things safer,
but they do take a lot more time to make changes or to get new items added. Do I think
there are potential inefficiencies in health care? I think just because health care is so big,
and it touches so many things.
P6 described a couple of reasons why the healthcare systems have complexities and
incompetencies. One of the significant factors is the use of different technology systems that
need to communicate with each other. The examples were the EHR having to interface with
various systems such as medicine cabinets where medications are stored, which meant building
drug records or any other components within the system. These pose a challenge in ensuring the
correct integration. Another example described by P6 involves the links between EHR systems
and intravenous (IV) pumps. Even though P6 stated that these links are beneficial as they
improve the healthcare process, implementing the changes or adding new interconnected items
can be time-consuming. These complexities arise from the need to ensure that the changes are
appropriately integrated and maintain safety and the effectiveness of care delivery. Some
inefficiencies may occur because of the vast scope of the healthcare industry with numerous
interconnected components.

126
P15, P9 and P6 affirm that health information technology system design and tools can
potentially have an impact on efficient usability by the clinicians, hence the need for
improvement. Kroth et al. (2018) suggested the need to redesign health information and
communication technologies as well as the clinical and architectural process in order to realize
significant improvements. Vehko et al. (2019) stated that health care organizations need to have
user friendly EHR systems and digital tools as well strengthen the clinicians e-care competencies
through organizational and regional actions.
P7 noted,
Yeah, exactly, it's because of the it's like I would say in a very short way, the lack of um
standard work um that you could I don't even duplicate because you don't want to
duplicate what's on paper, but at least if there were standards out there and better ways to
utilize the electronic record, it would be easier to kind of teach too and become more
efficient. But there's a lack of standards. It's difficult for people because they have their
way of doing things, um, kind of like, you know, like outlook, if you've used outlook, it's
a very good system. But do you think everybody takes advantage of all the wonderful
things there? Because, you know, it's complex, right? And you almost have to take a
class. I think a lot of folks have done that to be able to fully leverage it. So healthcare is
infinitely more complex than that. And so that's where the complexity and inefficiency
are coming to be able to teach to those standards is it's difficult. It's just difficult because
of the complexity.
P7 acknowledged the significance of the healthcare industry's complexity as a challenge
in the efficient management of HIT. Due to healthcare organizations size and complexity, there

127
is a major challenge surrounding realistic goals and timelines while managing the eminent
change needed for existing individuals, systems, and processes (Meinert et al., 2018).
Theme 4: Users report more potential than actual impacts on reputation.
Most participants noted that inefficiencies in the management of health information
technology have the potential to affect the organization’s business reputation in some ways.
However, five participants stated that there was no business impact. As noted by the participants,
the factors that would contribute to this were unfavorable external organization rating system
down, clinicians’ complaints about the system design, time impact of documentation,
information falling through the cracks, and waiting for update fixes.
P20 noted,
That I this could um and the management of I T. Um could potentially cause a negative
impact of the organization's business reputation would be you know around what I would
call you to know some of the reading's um and report cards that we receive on the
adoption of the EMR. So, things like an organization like hymns, healthcare information
management society, um, they have a state staging rating of the organization's adoption
of technology specifically in EHR um focused a lot on the reduction of paper and
efficiency and use of the electronic health records you know um as you know a leader
kind of in the industry for safety as well as quality outcomes um you know and user
satisfaction. So what I would say is that if you have a management team, you know that
that isn't plugged into, you know, kind of how you're rated in the industry, you would
potentially, um, either if you had achieved um, like a hymns rating, so he seven is the
maximum rating you can have like me general has that um for both outpatient and
inpatient um EMR adoption but if it's not something that you're mindful of and managed

128
to your ratings could slip, and that could impact um the organization negatively as far as
the reputation goes.
P20 supports that having progress evaluation in place can help healthcare organizations
with improvement and efficient management of health information technology. In light of
imminent challenges in adopting health information technologies like electronic health records,
several opportunities to develop more effective evaluation methods have promoted efficient
progress (Colicchio et al., 2019).
P12 noted,
The second part I'm getting at is the gap between the two. Um, when the technology isn't
there to support uh safety administration processes, which was a huge risk. Um, we've
seen it before because even on the original system, if we had downtime, we had the
system so long, they were likely nurses on our nursing units that went to school and never
documented ministry administration on paper. And so, when it came time for downtime,
and you got to switch to paper, um, those of us that had documented meds on paper knew
exactly what it meant to highlight a red and yellow or a circle of time and read, but that
meant nothing to people that never did it before. So, it became a real um not only a safety
concern about, you know, properly a knowing which meds to administer and
documenting it appropriately. Um, but be the time it added to doing that administration
because people weren't familiar with the process.
P12 concurs with the importance of issues with technology needing to be tailor-made to
ensure safety is addressed. This can pose a considerable risk to healthcare delivery. HIT care
provides safe and efficient care delivery. It can also pose challenges involving design and
development, implementation and use, monitoring, and optimization (Sittig et al., 2020).

129
Representation and Visualization
Data Analysis Summary
Table 1
RQ1 Theme 1 Table
Theme
Code
Files
References
Theme 1. Users face a range of
management challenges leading to
inefficiencies
20*
34*
accuracy of user entries-coding
3
4
communicating technology
standards
1
1
documentation
2
3
federal policies-rules
1
1
information access across
systems
3
5
optimizing for the whole team
1
1
potential for provider error
1
1
privacy-security of health
information
1
1
resistance to adoption
1
1
software defects
1
1
training to learn the system
7
8
transition from paper to
electronic
5
6
updating of work queues
1
1
* Indicates an aggregated total

130
Table 2
RQ1 Theme 2 Table
Theme
Code
Files
References
Theme 2. A range of strategies
used to ensure efficient
management of HIT
19*
25*
audits by health information
management team
1
1
early adoption stakeholder
analysis
1
1
effective indexing of paper
documents
1
1
ensuring workflow efficiency
2
2
frequent IT meetings
1
2
huddling and project
management
1
2
modified system to fit
practice
1
2
policies and procedures
7
7
smooth change control
processes
1
1
staff involvement and training
5
5
using best practice standards
1
1
* Indicates an aggregated total

131
Table 3
RQ2 Theme 3 Table
Theme
Code
Files
References
Theme 3. Management of issues
lead to disruption in efficient
delivery
19*
21*
backgrounds and training of
senior leadership
1
1
customization makes upgrades
challenging
1
2
design of tools
4
5
different style of practice
1
1
inefficiencies due to
complexity of healthcare
4
4
lack of standards in data
sharing
1
1
limits of product
customization
2
2
prioritization of ticket to fix
issue
1
1
rules are confusing and
constantly changing
1
1
unannounced changes during
updates
1
1
user inaccuracy
2
2
* Indicates an aggregated total

132
Table 4
RQ3 Theme 4 Table
Theme
Code
Subcode
Files
References
Theme 4. Users report more potential
than actual impacts on reputation
18*
20*
no impact on business reputation
5
5
potential impacts of disruption on
business
13*
15*
clinician complaints about
system design
2
2
external organization ratings
3
3
inaccurate information
1
1
information falling through
cracks with updates
2
2
number of steps-amount of
resources
1
1
system downtime
3
3
time impact of documentation
2
2
waiting for updates-fixes
1
1
* Indicates an aggregated total
NVivo note references coded indicate the number of data references that was coded to the
identified theme and % coverage indicates the percentage of data file that coding represents.
Relationship to Findings – How They Relate to Key Areas in the Research Proposal
Relationship to Research Questions
Research Question 1. How has the mismanagement of health care information
technology within health care organizations led to medical errors which resulted in the disruption
of health care delivery?

133
This question seeks to understand how the inefficient management of health information
technology has led to medical errors disrupting quality healthcare delivery.
Research Question 1a. What are the Electronic Health Records management issues that
contribute to medical errors?
This sub-question specifically inquires how the mismanagement of health information
technology with a focus on EHR has resulted in medical errors impacting the delivery of quality
care. It has been shown that while EHR have contributed to the improvement of coordination and
improvement of healthcare, they can also pose some risks to the patient stemming from their
inefficient design and implementation, inadequate information to support user awareness, lack of
monitoring, and efficient management (Palojoki et al., 2017).
The finding corroborates the users face various management issues, as shown in the
theme 1 table under the representation and visualization section. These issues were referenced 34
times. The highest included training to learn the system, transition from paper to electronic,
information access across the system, and accuracy in user entry. Koppel and Kuziemsky (2019)
stated that HIT useability issues remain predominant, leading to adverse outcomes in care
delivery. Findings in RQ1 are also demonstrated under the theme 2 table in the representation
and visualization section, where participants provided a range of strategies used to address the
management issues faced by the organization. The two predominant strategies were applying
strong policies and procedures and staff involvement and training.
Research Question 2. Why has the mismanagement of health care information
technology negatively impacted patient safety and resulted in the disruption of efficient delivery
of health care?

134
The purpose of this research question is to understand why the mismanagement of health
information technology has negatively impacted patient safety, resulting in the disruption of
efficient healthcare delivery. According to Wang et al. (2019), not efficiently managing health
information technology impacts the healthcare organization's clinical decisions and care process
and results in outcomes that can potentially harm the patient due to clinical errors.
Theme 3 table under the representation and visualization section confirms why the
mismanagement of health information technology occurs leading to the disruption in care
delivery. Most participants stated that it was due to the design of tools and the complexity of
health care. According to Hose et al. (2023), HIT design involves the integration of multiple
perspectives due to the diverse roles.
Research Question 3. How has the mismanagement of health information technology
within health care organizations led to the disruption of quality health care delivery resulting in
medical errors and negatively impacting business reputation?
This question seeks to understand how the mismanagement of health information
technology within the healthcare system has disrupted quality healthcare delivery, resulting in
medical errors, and impacting the organization's business reputation. Management issues arising
from health information technology are due to the reason that it is not designed, implemented,
monitored, and managed efficiently to ensure the safety of the patient and provision of quality
care resulting in the potential negative impact on the firm's business reputation and return on
investment (Sittig et al., 2020).
Theme 4 table under the representation and visualization section shows more potential
impact on the organization’s business. Even though five participants reported no actual impact,
the majority stated that there is a high potential, especially concerning external organizations’

135
ratings and system downtime, which can cause the information to fall through the crack and
impact the documentation time. This factor corroborates that HIT management issues are due to
a lack of good design, implementation, and monitoring to ensure quality delivery, potentially
impacting the organization’s business (Sittig et al., 2020).
Relationship to the Conceptual Framework (see Figure 1)
The conceptual framework helps organize the structure for research design, data
collection, analysis, and interpretation (Lynch et al., 2020). The findings in this study, as
illustrated in themes one, two, and three, confirmed that the inefficient management of health
information technology is attributable to the respective elements of the conceptual framework
used in this study. They are concepts, contrasts, actors, and theories. The study confirmed the
concepts of interoperability concerning information across systems: implementation and
usability due to issues with the transition from paper to electronics. Contrast use acceptance
resulting in coding errors. Theme two confirmed the contrast in issues related to system design
and tools and user accuracy. Theme four further corroborates that with systems frequent down
time, care delivery can be negatively impacted. Participants noted that even though there are
backup plans in place, when the system goes down it can cause some delays in care delivery and
result in some serious issues.
P10 noted,
When the technology isn't there to support uh safety administration processes, that is a
huge risk. Um, and we've seen it before because even on the original system if we had
downtime, we have the system so long, they were likely nurses on our nursing units that
went to school and never documented ministry administration on paper. And so, when it
came time for downtime, and you got to switch to paper, um, those of us that had

136
documented meds on paper knew exactly what it meant to highlight a red and yellow or a
circle of time and read, but that meant nothing to people that never did it before. So, it
became a real um not only a safety concern about, you know, properly a knowing which
meds to administer and documenting it appropriately. Um, but be the time it added to
doing that administration because people needed to become more familiar with the
process.
P10 raised concerns about system downtime, which can delay and affect efficient care
delivery. Larsen et al. (2020) supported the idea that downtime can result in delays that can
translate to safety issues for the patient. Planned downtime may occur to correct hardware issues,
software errors, computer viruses, and other attacks. Planned downtime usually is scheduled
during low-impact hours, and healthcare providers are generally informed in advance.
The element of training is highly confirmed regarding training issues in theme1, 2, and 3,
as shown in the representation and visualization section. Rahman Jabin et al. (2022) stated that
lack of adequate training and competence are some of the factors contributing to healthcare
professionals' lack of awareness of health information technology issues. In theme one,
Participants highly confirmed training issues with HIT and stated that it affected their ability to
carry out their clinical duties effectively.
P11 noted,
From the beginning, one thing that was taught is that nurses should only document in the
checklists that they should not be putting um handwritten notes or typewritten notes. If
you compare notes, they should have only been using the check box, and it took quite
some time for us to undo that philosophy. Because we needed to include the event details,
you can only capture important details by having a written narrative. We still run into

137
people who believe they shouldn't write anything wrong in the chart. So, we spend a lot
of time again re-educating that narrative notes are not only necessary but, you know,
everyone needs to understand what the details of a situation are. So, the first issue we had
was training and staff competency, and I'll go into some; for example, we had a lot with
the old, filled record. There wasn't a lot of higher education required because it was a
paper, we were managing paper um and when we went to the EMR, of course, you had to
learn a new skill and learn the computer, and so we had some folks who really struggled
with that but just were not equipped for that. Um, that big of a change. It takes several
months to learn the system. And so, during that time, you can't be as productive. So, we
saw half the number of patients we ordinarily see for a month after we installed Epic.
P11 described how before implementing electronic medical records systems, nurses were
taught to rely solely on checklists for documentation and not handwritten or typed notes. This
process posed an initial challenge as it was difficult for the nurses to overcome, resulting in
spending a significant amount of time re-educating to rely solely on a checklist versus
handwritten notes. The primary challenge revolved around training and staff competency
because, in the past, when paper records were the norm, minimal education was required to
perform the tasks. Transitioning to an EMR system like Epic required new skills and computer
proficiency (P11). P11 stated that learning EMR took months, slowing the transition from paper,
impacting productivity, and reducing the number of patients that could be seen.
P19 noted,
So, there's educational learning theory around this, and there's no difference; try to train
positions and staff around it. Um, so that's how we did it in different pathways and at
different times. Um, and then at the elbow support when folks start using it so that we

138
call it just-in-time training, meaning you get information just as you need it, which is not
listened to. Still, it's needed because you can only absorb so much and invariably come
across things you didn't know or didn't know. The biggest issue is more inefficiency, um,
and that that is, that just stops folks in the tracks, they can't get the same work done
because they don't know how or they can't do it efficiently, takes them three times as long
to do the same task, and that could, you know, that can lead to delays. We don't want that
to happen, either. So yes, errors could happen, but it's mostly how to get things done,
which leads to slowing down and inefficiency.
P19 said an educational theory was applied to address the challenges and promote
effective learning with EMR systems. The goal was to train different positions and staff
members according to their specific needs at various implementation stages. This approach
recognized the importance of tailoring to individual roles and providing “just in time” training to
ensure that relevant information was provided to staff members when actively using EMR. Even
though the training was offered, there were still some inefficiencies due to staff members
performing their tasks efficiently as they often encountered roadblocks that hindered their
productivity (P19). Some efficiencies, as described by P19, were related to many interfaces
connecting EMR with other systems. Even though efforts have been made to standardize Epic
with many interfaces, it is still challenging to achieve universally. Since most interfaces are
regularly maintained, there are minimal errors in data transmission to the EMR.
P11 and P19 corroborate the need for more training, especially regarding the transition
from paper to electronic. They state that they can avoid things falling through the cracks if done
efficiently. Magruder et al. (2018) stated that while electronic health records are beneficial in
maintaining health care records, its transition from paper to electronic can be very costly

139
regarding staff training and implementing the software required. One of the main factors
impacting clinicians' efficient use of health information technology is the need for adequate
training, policies, and technical support (Rahal et al., 2021).
In theme 2 participants confirmed that training is a necessary strategy used to ensure the
efficient management of health information technology.
P16 noted,
Some of the things that occurred during our implementation were a lot of training
specifically targeted at physicians. one on one training classroom training follow-up
training. Um, and then um, a whole new department was created um for clinical
informatics during the go-live where an informative could go meet with the physician
round with the physician support them as they learned and managed through whether it
was documentation or ordering or um you know any anything like that where they could
get 1 to 1 essentially hand holding. The second thing we developed at the same time
helped, specifically for physicians. And so, um, perhaps you were feeling confident, but
then all of a sudden ran into like, I'm ordering this med. I can't figure out why it won't let
me place my order or whatever issues they might run into um, or maybe they didn't even
know how a lot of times with some of the meds, it can be at least early on could be tricky
like if there was a sliding scale or the reconciliation process. And so anyway they could
maybe they were confident except for this one thing, then they could call the help desk
and ask very specific clinical questions which we managed that help desk with strictly
nurses.
In theme 3, several participants stated that the experience, backgrounds, and training of
senior leadership would yield an efficient impact of the management of health information

140
technology. This corroborates with the component of health care leader in the sense that hold the
key role in ensuring that the problem stemming from management issues in health care
information technology which may result in the disruption of health care delivery are effectively
dealt with. Saranto et al. (2019) noted that leadership is an essential factor in the management
and success of the organization's projects because it drives people, partnerships, resources,
processes, strategy, and planning.
Theme 3, indicating inefficiencies due to complexity, corroborates with the Actor-
network theory as it studies the relationship that links people in dynamic networks of position
practices. P8 noted, “So healthcare is infinitely more complex than that. And so that's where the
complexity and inefficiency is coming to be able to really teach to those standards is it's difficult.
It's just difficult because of the complexity, complexity.”
P8’s expression of the complexity of health care making it challenging to have efficient
HIT corroborates what Lehne et al. (2019) described as the current healthcare infrastructure with
health information comprising various forms, making it difficult to process.
Theme 4 confirmed the importance of the use of policies and procedures as a means of
managing health information technology efficiently. This finding corroborates the diffusion on
innovation theory, which, according to Ljubicic et al. (2020), focused on analyzing channels of
communicating innovation among members of the organization in each unit to help determine its
adoption, value, compatibility, and consistency with the organization’s existing processes,
complexity, and operability. It is because it reinforces the importance of understanding critical
aspects of efficiently dealing with the adoption, implementation, and use of health information
technology as it impacts how healthcare professionals manage it in providing quality care
delivery.

141
P13 noted,
We have a lot of governance around our technology. Um, we have it called the clinical
oversight committee. So anytime we are upgrading or touching any technology that
would impact the greater good, we take it there, so there's governance around it. Um, it's
not just me making the decision and saying this is what we will do. It goes to a committee
to agree upon to make sure it's the best for the organization. It's not something that is like
one person once or one specialty once. So um, we have a lot of governance around our
technology and what we put in our electronic medical records.
P13 further noted, “We have executives, a chief medical information officer, and a chief
informatics officer. That's not a physician. And then we have committees under them that, uh,
that help to optimize and create.”
P13 affirms that having good policies and procedures in place can help ensure efficient
health information technology management. Good management and governance are necessary
ingredients for the successful implementation of health information technology (Sligo et al.,
2017).
Relationship to Anticipated Themes
The data analysis for this study resulted in four major themes: (a) users face a range of
management challenges leading to inefficiencies, (b) a range of strategies is used to ensure
efficient management of HIT, (c) management of issues leads to disruption in efficient delivery,
and (d) users report more potential than actual impacts on reputation. Each theme comprises
several components, as shown in the representation and visualization section. In theme 1,
training to learn the system, information access across systems, and accuracy of user entries
coding were highly anticipated in the study. The transition from paper to electronic, even though

142
it was anticipated to a minimum level, resulted in more references. For instance, the findings
confirmed problems with information access across systems, hence, corroborates with the
elements of this anticipated theme as illustrated in the conceptual framework of this study on
interoperability, usability, and other minor issues on system upgrades.
P10 noted,
More current issues that can be discussed. Um Gosh, we have a number of interfaces to
other systems, but we've tried to standardize on epic for a lot, but not for everything. So,
but most of the interfaces stay up there and are regularly maintained. So, there aren't
many interface-related errors of data transmittal into the EHR, um, you know, downtime
is extremely rare at this point and usually only scheduled downtime for upgrades. So,
downtime procedures are usually handled fairly smoothly as well. So, I would say at this
point, um, and again sort of a function of going to unified medical records.
P10 noted,
So, the days I would have my chart for the patient, the endocrinologist would have their
chart for the patient. The cardiologist would have their chart for the patient in the hospital
and its own chart for the patient for admissions. And those were like, you know, four
separate puddles of information all about the same patient. Um, so as we've all started to
use the same chart and tried to go through some of that conversion process, um, I might
have a diagnosis for diabetes in the chart. The endocrinologist might have a more refined
diagnosis of diabetes or one that they want to use and not use mine. But they don't want
to delete mine, you know, the same thing with, you know, heart failure for me and heart
failure for the cardiologist. Uh, and then you know, what did the patient actually get
admitted for in the hospital? And what, you know, problems did the hospitalists choose to

143
put on the chart? Um, and uh, particularly trivial things that affected the hospital stay,
like an elevated potassium level, um, that may have resolved and was never taken off the
chart. So, it's now noise on my problem list when they get back to the office. So too many
cooks stirring the pot.
Regarding current issues related to electronic medical records, P10 stated there were
many interfaces connecting EMR with other systems. Like P19, P10 stated that although efforts
have been made to standardize the Epic software for many interfaces, it has yet to be achieved
universally. Most interfaces are operational and undergo regular maintenance to minimize errors
and reduce downtime, which is also usually handled smoothly and efficiently. Implementing
unified medical records has resulted in more centralized patient chart information. In contrast,
healthcare providers maintained separate patient charts in the past, making it challenging to
consolidate the data. During the conversion process, issues arose from differing diagnoses and
duplicate information (P10). To address the challenges surrounding unified EMR, P10 suggested
the need for coordination, effective communication, collaboration, and data management to
enhance the quality and accuracy of patient information.
Another confirmed component that participants demonstrated was usability and
implementation issues that arose due to the transition from paper to electronic.
P16 noted,
The majority of issues leading to confusion and potential error, but I can't necessarily
come up with a definitive uh instance of that from my own experience, is the conversion
of information from the prior paper chart into electronic records. So sometimes providers
would do that, but more often, there was a pool of groups known as abstract. Urn, these
were usually people from health information management (HIM). They at least had some

144
familiarity with looking at charts which would take a stack of paper charts and try to copy
over some core information as best as they could glean from the paper chart. Things like
medication problems, allergies, and sometimes immunizations, past immunizations, were
the most common things they would have to type in many respects. Um, so any time you
do manual data entry, area of the potential for missing things, misinterpreting things, or
accidentally entering the wrong thing. Um, I'm sure that happened.
P16 described the primary source of confusion and potential errors, especially during the
transition from paper to electronic health records. The providers did the primary task of
conversion. It was often handled by the team from health information management (HIM), who
were familiar with reviewing the charts. They would transfer patient information from paper
charts into the electronic system. The challenge with this is that there is always a potential for
error whenever manual data entry is involved. Although precautions are taken to mitigate these
issues, it is acknowledged that instances of mistakes still occur around the conversion process
(P16).
P14 noted,
Alright. This one, at the time that we implemented our epic or electronic health record, I
was over transcription. Um, so I had a yeah, I had a staff of 80 people. So, for us, it took
away their work. Um, and then our staff started seeing the position self, the reports they
completed themselves. It was really hard to keep my staff focused on what they were
doing because they were so quality driven to make sure the reports that were in, you
know in our health record were as good as possible. As you know, the best quality, and
then they see, I'm going to put, for lack of better words, junk that the doctors were

145
having. And that was really hard from a management perspective to get them to say,
‘Okay, you can't worry about that; you worry about our piece of it.’
When implementing electronic health records, P14 stated that they were responsible for a
team of 80 members whose primary responsibility was transcribing medical reports. With the
introduction of electronic health records, their role and workload changed significantly. The
automated nature of electronic health records replaced the need for manual transcription. This
shift in responsibilities presented challenges as the staff members needed help to balance their
commitment to quality with their primary duties. Establishing clear priorities and emphasizing
the importance of specific tasks became crucial in ensuring their focus remained on the
designated responsibilities.
P3 noted,
Well, for our department, my department is clinical coding; for the coders, their biggest
concern, and maybe what you want to call an obstacle, was the concern that the providers
were doing a copy-paste, just moving information from one encounter to the other
without verifying it and confirming that the patient still had these issues. So that's always
been a concern, the copy-paste.
P3 described their departments as being responsible for coding. With that being said, P3
stated that coders expressed significant concerns and obstacles regarding the practice of copy and
pasting by healthcare providers. This process involves transferring information from one patient
encounter to another without verifying its accuracy or confirming whether the patient still has
documented health issues. Coders emphasize the importance of healthcare providers verifying
the relevance and accuracy of the information they copy and paste. P3 strongly recommends
applying efforts such as education and raising awareness among healthcare providers about the

146
potential risks associated with copying and pasting, encouraging healthcare providers to assess
the information they transfer critically, verifying its accuracy, and updating to mitigate the
challenge, additionally, implementing monitoring systems or auditing processes to identify
instances of excessive or inappropriate copy and pasting to contribute to maintaining data
accuracy and reliability.
P17 noted,
The first thing that comes to my mind is more related to my time as a bedside nurse. The
most common thing, and I still see this today, um, as a manager, is when the electronic
medical record makes things too easy. And users take the first for the most obvious
choice when it's only sometimes the right one. So, I'll give this an example, um, when
administering medication. Um, Sometimes, um, nurse providers will get used to the way
EMR works. And so, they type in the first couple of letters of the medication or
something along those lines, and you get a bunch of quick options. They take the first
one, and maybe that's been right most of the time, but this time it wasn't, um, and that's
usually what can lead to, um, the most medical errors in my mind in the outpatient
setting. We see this in um ordering as well. Uh, sometimes a provider will go to put in an
order, and they're starting to type their order in; the first option that comes up is the right
one when it's not.
P17 described the reoccurring issue that can create a challenge with the use of EMR as
the tendency for the healthcare provider to opt for the first choice without thoroughly considering
all available options, as this practice can lead to errors in medical documentation and
inaccuracies in ordering medications. To address this issue, P17 stated that healthcare
organizations must promote a culture of attentiveness and double-checking when using the EMR

147
system, encouraging users to review all available options carefully and add training programs
and educational initiatives that can emphasize the importance of critical thinking and verifying
choices to ensure patient safety in both inpatient and outpatient settings.
P10, P11, P14, P3, and P17 concur that electronic health records pose challenges with
useability, acceptance, and implementation. Electronic health records have a unique interface and
approach to representing and storing clinical information with minimal data sharing (Mamlin &
Tierney, 2016). Implementing HITs, such as electronic health records, can produce positive
outcomes. There are some challenges related to useability and human factors. These useability
issues affect all other clinicians and may lead to medical errors (Carayon & Hoonakker, 2019).
The implementation concept affects the efficient management of health care information
technology for reasons such as user acceptance, motivation to use the system, confidence,
support, integrity, and sharing of information to improve patient care and overall health care
delivery (Wang et al., 2019). One of the ordinary everyday actions made possible through the
electronic health records system, such as copy and pasting, may cause a typographical error to be
copied repeatedly. Such can result in many mistakes, leading to a medical error that can harm the
patient (Colicchio et al., 2019). Overloads in EMR have caused specific errors related to
usability. Complex user interfaces make it more challenging to navigate the EMR and can
increase the likelihood of erroneous orders for medications, testing, and other interventions
(Nijor et al., 2022).
Even though other components such as communicating technology standards, potential
provider error, privacy-security of health information, and resistance to adoption were
anticipated, they resulted in lower references, as shown in the theme 1 table. Policies and
procedures and staff involvement in theme 2 scored as highly anticipated, as reflected in theme

148
table 2. Receiving workflow efficiencies audits by health information management, early
adoption by stakeholder analysis, huddling, and project management was highly anticipated in
this study but revealed lower references. In theme 3, the component of the design of tools was
highly anticipated for this study; however, the inefficiencies due to complexities of health care,
even though not highly anticipated, resulted in more references, almost to the design of tools.
Other components, namely: senior leadership background and training and lack of standard data
sharing, were highly anticipated but came short as shown in theme table 3. Other unanticipated
components revealed in this theme included customization, which made upgrades challenging,
prioritization of tickets to fix issues, and rules confusing and continuously changing. Theme 4 of
no impact on business reputation was referenced five times but was not anticipated in this study.
However, 15 references confirmed there was a potential impact on the organization’s business
reputation. The sub-components that were highly anticipated included external organization
rating, system management not working efficiently at times due to downtime, clinicians’
complaints about the system design, and time impact on documentation. Anticipated sub-
components such as inaccurate information, number of steps of the resources, and waiting for
updates had lower references than anticipated. The anticipated component of the themes
referenced by more participants in the findings was related to training, hence, it has dominated
all sections of the presentation of the findings and additionally corroborates with the conceptual
framework of this study.
Relationship to Literature
The components in theme 1, which highly corroborate with the literature, include
information access across systems, training to learn the system, and transition from paper to
electronic. This theme illustrates that users face various HIT management challenges leading to

149
inefficiencies. For instance, the lack of information across systems corroborates with the
literature on interoperability. Adams et al. (2017) and Alotabi and Federico (2017) stated there
are concerns about interoperability, which without, patient safety can be impacted. Rudin et al.
(2017) agreed that innovative technologies help address health care coordination for complex
patients. It states that there are challenges concerning functionalities due to a need for
interoperability between coordinate systems. Training to learn the system scored even higher in
the confirmation of literature. In order to meet the challenges with the use of technology, there
has been a development of new treatments, higher training of health care professionals, the
establishment of efficient facilities, and information technology (Shi & Singh, 2019).
Regarding information technology training, since health care providers have to work with
various hospitals with different kinds of health care records, they need help to learn and remain
proficient with every software. Because of that, they tend to utilize the ones they are more
familiar with (Carayon et al., 2012). These issues have delayed the transition from paper to
electronic, resulting in accuracy issues of user entry coding. Theme 2 provided a range of
strategies to ensure efficient health information technology management. Policies and procedures
were significantly used to ensure efficiency. According to Meinert et al. (2018), it is widely
believed that key challenges with health information technologies are not only the design or the
innovation but the lack of policies and framework that can enable its adoption, sustainability, and
its capability to be used in a wide range of functions in health care. The component of staff
involvement and training is once again reflected in theme two as it was in theme one and
corroborated with the literature. As stated by Rathert et al. (2019), inadequate training on EHR
impacted clinicians' ability to communicate and coordinate efficient care delivery. It is critical
that hospitals commit to regular system upgrades and the required training for all users to reduce

150
the risk of potential medical errors (Palabindala et al., 2016). Theme 3 provides components
showing management issues that have led to efficiencies in HIT. The design of tools
corroborates with the literature, as echoed by Demiris et al. (2019), that innovative tools have
increased health care support.
There is a need to understand their effectiveness and design and implementation
strategies to accelerate their utility and user acceptance. Today's market health care organizations
worldwide are substantially investing in designing and implementing health information
technology such as dashboards, status displays, clinical decision support, and other patient-facing
technologies (Carayon & Hoonakker, 2019). The inefficiencies in HIT are due to the complexity
of the health care industry, corroborating with the literature. Carayon et al. (2012) stated that the
complexities of the health care industry can lead to management issues because of the various
hospitals where providers work with different types of HIT, making it difficult to be proficient.
Theme 4 illustrates there is more potential impact on the business if HIT is not managed
efficiently, corroborating with the literature.
According to Sittig et al. (2020), it is clear that the widespread adoption of health
information technology results in potential benefits. If not managed efficiently, it can disrupt the
delivery of quality care, negatively impacting the business reputation. Clinician complaints about
system design corroborate the literature on physician burnout related to HIT, where they
experience poor functionality, more consumption, and inefficient information (Heponiemi et al.,
2017). These affect efficient management and care delivery provision, potentially affecting the
business's reputation. One more significant component not explicitly found in the literature but
confirmed that it could have some potential impact on the business reputation was that of the
negative external organization rating. Participants indicated several reasons physicians and other

151
clinicians complained about health information technology and why they felt it led to burnouts
that could impact quality care delivery and negatively impact the organization’s business
reputation.
P1 noted,
So, my opinion on this one is that technology has created. Well, first of all, we have
physicians who count clicks that started early on; somehow, they found, you know, I've
got to get to seven clicks before I can get to the end of my task. Um, and so we spent a lot
of time on that. But also, there are a lot of efficiencies built into the electronic medical
record to create um safety measures such as drug allergies. So, I'll use myself as an
example. I'm allergic to penicillin. And so, if somebody tried to prescribe penicillin, the
electronic medical record would flag, you know, flag it for the position that says this
patient has an allergy. Are you sure you want to proceed? And what happens often is that
they go right past it. So, the original efficiency and safety that was supposed to be present
because it was smart enough to say, I can tell you right away. Is this patient allergic to
penicillin? They're so in tune with how many clicks and I can't be bothered with clicks
that they ignore them. Oh, not every physician does that, but the ones who do it, boy, it's
scary.
P1 further noted that another example was duplication.
So, we have a lot of stuff built into the system that perhaps you're rounding in order
penicillin, which is a bad example. You're rounding a new order, um a test, X-ray and
then I come in two hours later as a different physician, a different service line, and I order
a chest x-ray. It will tell me the second person that's a duplicate order. Are you sure you
want to proceed? And again, sometimes what will happen is I don't have time to be

152
bothered with what that box or that banner says, I'm just going to click right past it, and
you know, things like that. And that creates inefficiency where it was supposed to create
safety and efficiency.
P1 corroborates that physicians felt that useability challenges and unique features of
electronic health records could contribute to inefficiencies in care delivery. Physicians feel that it
poses challenges related to efficient navigation, additional time to execute documentation in it,
and the increased number of clerical tasks such as data entry they have to do (Gardner et al.,
2019). Some features of EMR features resulted in errors that included typos, adding information
to the wrong patient chart, and not intentionally selecting an incorrect item in the diagnosis or
medication (Rahal et al., 2021).
P2 noted,
It’s had a positive and a negative impact. I think the negative pieces that are, you know,
making it into the news, um, if you ask anybody in healthcare, they would, they would
never want to go back to paper and the way it was before because I know we have a
better quality of care now. The main difficulty we hear the most vocal complaints about
is that many of the systems weren't designed around the providers of care, making it easy
for them to do their job. It was around billing and documentation and parts of the
business that are part of the business. Still, they're away from the people actually using
the technology. So, there it's slowly getting better, but primarily it wasn't, I think really
designed for the clinicians at heart um, and so that's, I think, where the complaints come
from, the reality is it's better than way better than being on paper. We have better quality,
better access to metrics um, definitely more legible and all sorts of positive, but inherent
difficulty with it is a design issue.

153
P2 agrees that the difficulty with the design of the HIT has a main impact in the efficient
use. Sittig et al. (2020) stated that health information technology has efficiently facilitated and
managed health care delivery. There are challenges, including the design associated with a poor
interface, which can lead to data input and comprehension errors.
A component of theme 4 that the participants highly referenced as having the potential to
have a negative impact on the organization’s business was that of the external organization
ratings. This component was not somewhat covered in the literature review of this project. The
findings revealed that it could play a significant role in inefficient health information technology
management. According to Benjenk et al. (2020), hospitals are rated on care coordination. The
components rated include mortality, readmissions, patient experience, compliance with evidence-
based guidelines, timeliness, and several other factors that increase the hospital's quality
performance. Because of that, hospitals are continuously seeking better ways of improving
patient outcomes. Thomas Craig et al. (2020) noted that hospitals' performance currently carries
a lot of performance owing to the growing demands to control healthcare costs. In the findings,
the hospital reimbursement was also noted by the participants at LGH as being based on reliable
quality care delivery and value to their patients.
P3 noted,
The management of I. T. Um could potentially cause a negative impact of the
organization's business reputation would be you know around what I would what I would
call you know some of some of the readings um and report cards that we receive on
adoption um of the EMR so um things like organization like hymns, healthcare
information management society um They have a state staging rating of the
organization's adoption of technology specifically in HR um focused a lot around the

154
reduction of paper and efficiency and use of the electronic health records you know um
as you know a leader kind of in the industry for safety as well as quality outcomes um
you know and user satisfaction. So what I would say is that if you have a management
team you know that that isn't plugged into you know kind of how you're rated in the
industry you would potentially um either if you had achieved um like a hymns rating so
him seven is the maximum rating you can have like general has that um for both
outpatient and inpatient um EMR adoption but if it's not something that you're mindful of
and managed to your ratings could slip and that could impact um the organization
negatively as far as the reputation goes.
P3 acknowledged the importance of having the organization's management enforce the
recognition and significance of organizational ratings to encourage and ensure efficiency. There
are legislations in place, such as the American Recovery and Reinvestment Act (AARA) of 2009
which mandates that healthcare organizations adopt certified EHR and achieve its meaningful
use. Otherwise, they can face penalties.
P4 noted,
And the medical record, specifically epic that we use, is extremely good at putting
information in and gathering information. Getting that information out in a usable way is
much more difficult. And how does that lead to disruptive quality care delivery and then
impact our reputation? Um, the hospital or the health system is evaluated on, um, the
quality care that we deliver, and that is measured um by very specific things. Like is the
population up to date with their colorectal cancer screening. Uh, have they had the proper
population of people have their mammograms, um for your patients with hypertension.
Um, is it in control, or do they have high blood pressure out of control for your patients

155
with diabetes? You know, does their uh hemoglobin A one C or how we measure long
term die? Uh, automatic control. Is it within range, or is it out of control? And so external
organizations look at all of these things and evaluate how we are as an organ, as a health
system. And so epic is really good at documenting that information. But then getting it
out is very hard and very nonstandard. Um, and so I think that is the biggest issue is that
there are no standards.
P4 further noted,
On the clinical side, certainly if the implementation or the design of the technology does
not support high-quality care, and I'm trying to think of an example to give you, um, a
lower quality rating or the negative outcome or sentinel event. You know, that's
something that, you know, something that adverse reaction was so severe. It had to be
reported. So those kinds of things can all obviously have consequences. Um, in value-
based reimbursement, where if your quality scores aren't as high as they should be, you're
going to get, you know, docked some payments. So, like for Medicare, they looked at the
readmission rate. If your readmission rates are too high, they cut a certain percentage of
the rate they pay you.
P4 corroborates that HIT implementation or design affects efficient use, leading to
undesirable care delivery. The implementation concept affects the efficient management of
health care information technology for reasons such as user acceptance, motivation to use the
system, confidence, support, integrity, and sharing of information to improve patient care and
overall health care delivery (Wang et al., 2019).

156
Relationship to the Problem
The general business problem in this study is that the mismanagement of health
information technology disrupts health care delivery which can negatively impact the
organization’s business reputation. Kim et al. (2017) stated that if not well managed, health
information technology in fully digitalized health care organizations can disrupt the delivery of
health care and result in threats of safety and harm to the patients. If health information
technology is not designed, developed, implemented, and managed appropriately, it disrupts
healthcare delivery and creates safety issues that impact healthcare organizations' quality of care
(Sittig et al., 2020).
The themes discovered in the data analysis confirm that management issues with health
information technology can potentially affect the organization’s business reputation. Theme 1
table demonstrates that users face various challenges with HIT leading to inefficiencies. The
major components of these challenges are related to training to learn the system, the transition
from paper to electronics, and issues with access to information across systems. Other medium to
minor challenges included the accuracy of user coding and documentation. Theme 2 presented
various strategies to manage health information technology efficiently. The components that are
significantly used are applying policies and procedures, reinforcing their use, and staff
involvement with training. Other less referenced strategies included ensuring workflow
efficiencies, frequent IT meetings, and project management. Theme 3 confirmed the problem
that management issues with health information technology led to the disruption of care delivery.
The significant components are the design of tools and inefficiencies due to the complexities of
the health care industry.
P21 noted,

157
Um, well, this is part of, you know, I think you can tell what my opinion is. Um, I don't
think the entire system was done with bad intent. Um, I think that was sort of guided by
well-intentioned goals of ensuring safety checks, like electronic and automatic safety
checks to prevent nurses and providers from ordering the wrong drugs or giving the
wrong medications. Um, but one of them, and I also think that it was guided by a goal of
performance improvement and being able to look back at the documentation and find out
exactly where errors occurred. So, I don't fault the people or anybody who developed the
system, but there's much of them to be had from the system. But one of the things that do
interfere with, um, my uh and other colleagues' documentation is a drive to make sure
that we have spent the appropriate amount of time on billable, on making sure that we
have documented billable diagnoses. And I've found that that has detracted from how
much time we can spend describing what is but more salient as providers. Um, so a lot of,
a lot of times the documentation seems like it's being written for um uh legal purposes
and or um billing purposes instead of as a, I think that probably the original intent was to
diagnose.
P21 acknowledged that developing electronic medical records systems was likely driven
by well-intended goals, particularly in enhancing safety checks and improving performance by
enabling retrospective analysis of errors. P21 stated that they do not believe that the entire
system was designed with malicious intent. Certain aspects of the system have revealed
unintended consequences and can hinder documentation practices. P21 described the challenge
clinicians have encountered with the use as being attributable to pressure to prioritize billable
diagnoses that often overshadows the need to capture critical medical details. To overcome these
challenges and ensure they don't interfere with the quality and purpose of documentation, P21

158
emphasizes the need to refocus on patients' needs and find the balance between billing
requirements and clinical documentation. By doing so, healthcare providers can ensure that
documentation remains accurate, meaningful, and aligned with the original intent of diagnosing
and treating patients.
P15 noted,
Let me see when we did have an efficiency. It was because the people who launched this
didn't know what they were doing or might have bought a product they didn't realize
didn't work for us. So, they have yet to ask us anything about how the product works. So,
there were a lot of inefficiencies with that.
P15 said that during the implementation of electronic health records, they encountered
significant inefficiencies attributable to a lack of understanding or decision-making by those
responsible for launching the system. P15 suggested that it seemed as though the system
launchers did not fully understand clinicians’ specific needs or acquired a product that was not
suitable for their organization. They failed to consult with the end users to gather insights on how
the system should function effectively with the workflow. These inefficiencies impacted various
aspects of their work process, causing frustrations and low productivity. P15 stated that they
experienced inefficiencies due to inadequate planning, lack of user involvement, and insufficient
consideration of their specific needs. These outcomes serve as a reminder of the importance of
comprehensive research, effective communication, and collaboration when implementing new
technologies to ensure optimal efficiency and productivity within an organization.
P21 and 15 affirmed that there have been many challenges with adopting health
information technology, resulting in negative impacts on efficient care delivery. With the
increase in the adoption of health information technology like electronic health records, there are

159
useability issues resulting in decreased productivity, workflow mismatch, and other patient
safety matters stemming from the design, which focuses on a single view making it difficult to
use for providers in care involving a group of patients. As such, they end up having to use other
supplemental methods, such as paper and memory, to make decisions on providing quality care
(Staggers et al., 2018). Rathert et al. (2019) suggested that the full potential benefits of electronic
health records have not yet been realized due to challenges arising from increased workload on
clinicians, provider overreliance on health information technology, interference with
interpersonal relationships, inadequate EHR training, and lack of trust of EHR information.
P18 noted,
So, that goes back to inefficient or poor planning. So, as I said before, we focused on
trying to make sure that we had, um, we weren't, we didn't wanna, the term we used was
paid the goat path. In other words, we wanted to do something other than automate
existing processes; we wanted to use this to deconstruct all the existing processes and
figure out how to build them more efficiently and safely. And then, as I said, build the
design and build the electronic solution around that. Um, I think again where there's a
lack of engagement um and or um a lack of um consultative resources to help guide,
reshaping or rethinking how you do something can be problematic and sometimes, you
know, it's I think um pretty well, at least in our organization universally understood that
you know, if you want to know how something, where should go to where it's being done
and talk to the people that are doing it, don't, you know, sit at your desk and assume you
know what's happening. And so, we made a concerted effort to try and bring frontline
staff to the table to talk about what's not working. And those conversations went pretty
well. It sometimes became harder because people had only ever done it one way, so their

160
thinking was constrained. Okay, well, how could I do it differently? And so even the
representatives from the health system and operations that were originally brought
together to do, um, we did uh, request for proposals from three major manufacturers had
to come in to do a demo. And um, one of the physicians said, you know, this is pretty
challenging because, um, you're giving us a blank sheet of paper and telling us to design
a car, but we've never seen a car. So, we have no idea where to begin. And so that's where
I think it takes some professional facilitation to help people think differently about how
they could redesign a process so that when you then go to the step of automating it,
you're supporting it, you're not, um, building in inefficiencies or potential quality issues
as you go.
P18 suggests that the inefficiencies surrounding HIT may be due to poor planning and a
lack of consultative resources. Health information technology has the potential to assist
healthcare providers in improving the quality of care through enhanced adherence to guidelines
and large-scale clinical monitoring within inpatient settings. In addition, healthcare organizations
use interactive self-serve cloud-based performance dashboards for business intelligence that links
strategy and performance across all types of users within healthcare organizations and beyond
(Kunjan et al., 2019).
Other issues included limits to product customization, upgrade challenges, senior
leadership background and training, prioritization of tickets to fix, and confusing rules due to
constant change. A few participants indicated and confirmed that there is a problem also
explicitly related to product customization with upgrades in health information technology.
P9 noted,

161
Um, within our electronic medical record, we went up on epic back in 2011 in, you know,
over the years, we've customized. And we're getting to a point where when Epic does
their updates when they do, they do quarterly updates to the system. So, they, um, they,
really look to the foundation of Epic. So, when we do upgrades, it's becoming more
challenging. The more we deviate from Epic foundation and customize it makes
challenging during those upgrades.
P9 noted,
Furthermore, when we upgrade the system, it's kind of like when you update your phone,
your cell phone, you know, to the newest and greatest um that quarterly, but they stick to
kind of the foundational and not, you know, they can't tailor to every organization um
customization. So, the more we customize, the more we get away from foundations, and
then the more kind of build and rework, we have to do to get our system back in the line,
which makes our upgrades longer.
P9 supports those challenges in upgrades and customization are other causes affecting
efficiency in useability. Healthcare organizations face great customization to meet the increasing
demand for services. These numerous challenges require organizational leaders to find solutions
that foster quality and cost-effectiveness. Accomplishing these solutions would require the
innovative adoption of EHRs at the bedside because it has the potential to provide practical,
patient-centered, quality nursing care (Walker-Czyz, 2016).
In theme 4, more users with fifteen references reported potential impacts on the business
reputation. The reasons why the business had the potential to be impacted were external
organization ratings, system downtime, clinicians’ complaints about the system design,

162
information falling into the crack, time impact to documentation, inaccurate information, and
waiting for update fixes.
Summary of Findings
In this study, the researcher investigated the problem pertaining to the mismanagement of
health information technology, resulting in the disruption of care delivery. Next, the researcher
identified and discussed current issues surrounding the inefficient management of health
information technology affecting quality care delivery and negatively impacting the
organization’s business reputation. The researcher assessed the steps healthcare leaders have
taken to mitigate the problem now and in the future. To do so, the researcher conducted
telephone interviews with Lancaster General Hospital participants, asking interview questions as
shown in Appendix A. These interview questions helped answer the following research
questions:
RQ1: How has the mismanagement of health care information technology within health
care organizations led to medical errors, resulting in the disruption of health care delivery?
RQ1a: What Electronic Health Records management issues contribute to medical errors?
RQ2: Why has the mismanagement of health care information technology negatively
impacted patient safety and resulted in the disruption of efficient delivery of health care?
RQ3: How has the mismanagement of health information technology within health care
organizations led to the disruption of quality health care delivery, resulting in medical errors, and
negatively impacting the organization’s business reputation?
The findings from the data analysis, as illustrated in the theme tables in the visualization
and representation section, confirmed a problem with the inefficient management of health
information technology and provided answers to the research questions. They demonstrated

163
various methods healthcare leaders have implemented to ensure efficient health information
technology management.
The findings from the first research questions confirmed that users face various
management challenges leading to inefficiencies and present strategies that the organization has
implemented to address the challenges. In theme 1, the findings from this question show that the
participants unanimously identified training as a significant challenge leading to the inefficient
management of health information technology. In supporting the efficient implementation of
health information technology systems (e.g., electronic medical records), there is a need to
develop appropriate user training and support for clinicians so that they can be competent in
using it for health care delivery as it is critical for success (Scott et al., 2019). Training again
scored high in the second theme as one of the strategies to manage health information technology
efficiently. Besides training, participants also unanimously identified using policies and
procedures as a strategy for efficiently managing health information technology. Hossain et al.
(2019) stated that certain specific issues must be supported with appropriate policies and
procedures to implement HIT, like electronic health records successfully.
The findings from the second research question corroborated that the management of
issues leads to disruption in efficient delivery. In the findings from the second research question
in theme 3, most participants are leading management issues in health information technology
leading to the disruption of care delivery as being associated with the design of tools and
inefficiencies due to the complexity of health care. These findings support the existing findings
regarding some key factors impacting the inefficient management of health information
technology, as illustrated in the conceptual framework.

164
Results from the third research question confirmed that the inefficient management of
health information technology potentially impacts the organization’s business reputation. The
findings from the third research question, theme 4, resulted in most participants identifying that
the inefficient management of health information technology could impact the organization’s
business reputation. The highest indicators they presented were the external organization rating
and system downtime. They stated that if the ratings are unfavorable, it could impact the
business’s reputation negatively, and the slow-down system could affect the efficiency in
delivering care, thereby negatively impacting the business.
Application to Professional Practice
This section analyses improving the general business practice and potential strategies to
apply for the efficient management of health information technology (HIT) at Lancaster General
Hospital (LGH) in Lancaster, Pennsylvania. This section evaluates potential strategies as shown
in the literature review, including any implications and suggestions realized from the interviews
with LGH participants. The findings in this study will benefit the healthcare professionals in
ensuring that they have the necessary training and functional HIT tools and applications to use in
the continuous provision of quality care, thereby positively impacting business reputation.
Improving General Business Practice
The general problem in this study was the inefficient management of health information
technology and what healthcare organizations have done to address this problem. The findings
from the interviews overwhelmingly revealed that the inefficiencies were due to issues related to
training and learning systems like electronic medical records. Inadequate training on electronic
medical records impacted clinicians' ability to communicate and coordinate efficient care
delivery (Rathert et al., 2019). Carayon and Hoonakker (2019) agreed that inadequate training on

165
EHR impacts the clinicians’ ability to communicate and coordinate efficient care. Carayon and
Hoonakker (2019) stated that lack of trust was attributed to inaccuracies in the data entered,
unclear notations, and delayed data entry. Rahman Jabin et al. (2022) noted that inadequate
training and competence contribute to healthcare professionals need to gain awareness of health
information technology issues. Health information technology enhances healthcare teams'
performance with increased data collection and information exchange efficiencies, thus leading
to cost savings therefore, it is essential to add training programs and educational initiatives
emphasizing the importance of critical thinking and verifying choices to ensure patient safety in
and out-patient settings (Gauthier et al., 2018).
In the interviews, the second most response on issues surrounding the inefficient
management of health information technology was due to the system design and tools, which
also encompassed customizations that participants felt were not tailored to the specific condition
or scenario, impacting documentation, quality, and efficiency. They expressed the need for
system designers to involve clinicians, midlevel practitioners, and physicians in designing health
care tools and systems. Vehko et al. (2019) suggested that healthcare organizations need user-
friendly electronic health records systems and digital tools that can strengthen the medical
professional's e-care competencies through organizational and regional actions.
The interviews' third most response was on methods the organization has in place to
ensure the efficient use of health information technology. Besides other forms of training
initiatives, LGH has implemented robust policies and procedures to govern the efficient use of
HIT. They comprise organizations' procedures for implementing upgrades or changes to the
system and proactive education of the users. Among other methods of ensuring efficient adoption
and use of health information technology by employees, organizations offer speedy procedures,

166
well-defined procedures, and support for teaching hospitals and career development. Capurro et
al. (2017) echoed that standards and procedures are critical components of strategies needed for
the successful adoption of HIT by stakeholders.
The efficient use of health information technology can result in benefits such as improved
quality care due to rapid access to patient information, improved productivity and financial
improvements related to efficient billing systems and the like (Khalifa, 2017). With components
of electronic health records with patient portals, it can facilitate timely health information
exchange (Health Information, 2020). If not efficiently managed, it can result in some
undesirable outcomes. To realize the potential efficient use, it is imperative to address the
challenges associated with health information technology (Sittig et al., 2018).
Potential Application Strategies
The findings of this study revealed potential major strategies healthcare professionals,
healthcare leaders, and system designers of HIT applications could implement to ensure the
efficient management of health information technology. The researcher's first strategy would be
to provide enhanced training in HIT for healthcare professionals and other stakeholders of LGH.
This training should be periodically updated based on continuous needs assessments. As
organizations are increasingly utilizing intensive technologies such as HIT due to digitalization,
one of the important influences is leadership support through cultivating and sustaining training
initiatives for regular, systematic training in health information technology (Giunti et al., 2019).
Organizations such as American Medical Informatics Association (AMIA) have taken
steps to provide comprehensive specialized training in informatics, thereby equipping healthcare
professionals with the necessary knowledge and skills needed to navigate the intersection of
healthcare and technology. This training helps them utilize HIT systems like electronic health

167
records, clinical support systems, telemedicine, and other HIT systems (Giunti et al., 2019).
Purnell (2020) noted that healthcare professionals like nurses who received medical informatics
courses had a much more positive attitude toward IT for healthcare delivery. Among some
incentives that hospitals use as motivators to enhance attitudes toward the acceptance of new
technologies are monetary rewards and game applications similar to the functions of health
information systems (Ifinedo, 2018).
The second potential strategy will require a planned, effective design of the system and
health information technology tools to accelerate its efficient use. Demiris et al. (2019) noted that
while HIT has increased healthcare support universally as they are increasingly being applied,
there is a need to understand its effectiveness and strategies to design and implement to improve
its utility and acceptance. There is a need to redesign health information communication
technologies and clinical and architectural processes to realize significant improvements
(Demiris et al., 2019).
The realization of health information technology to promote healthcare delivery
efficiencies also relies on addressing other nontechnical challenges and prioritizing user
involvement (Tang et al., 2018). User-centered design is a critical strategy in achieving this
objective as it enables designers to understand the user’s perspective, experience, and needs.
Through the involvement of users, HIT applications can be tailored to meet their specific
requirements, thereby increasing the effectiveness and overall success of care delivery (Tang et
al., 2018).
The third potential strategy will be to increase communication and collaboration among
healthcare professionals and their information technology departments. Effective communication
helps an organization run efficiently (Alsaadat, 2019). Ennis-Cole et al. (2018) noted that

168
collaboration and networking have become essential for professionals across various industries.
Other factors, including geographic distance, can pose a challenge. Collaboration is essential for
overcoming usability challenges with health information technology; this requires a collective
effort, shared responsibility, and collaboration among various stakeholders (Ratwani et al.,
2019). With video conferencing tools, organizations can utilize virtual face-to-face presentations.
Such a tool would allow healthcare professionals and other stakeholders to host meetings and
presentations. This type of communication technology enhances convenience and opens
opportunities for collaboration and knowledge sharing in information technology (Ennis-Cole et
al., 2018).
Summary of Professional Practice
The efficient use of health information technology can result in better care delivery,
greater productivity, and business success. If not efficiently designed, developed, implemented,
and managed, it can create issues impacting healthcare organizations' quality of care (Sittig et al.,
2020). The findings in this study revealed that training issues with HIT significantly contributed
to inefficient use, thereby impacting the clinicians' ability to communicate and coordinate care
efficiently. As revealed in the findings, another major factor surrounding the inefficiencies in
HIT is the design of HIT systems and tools, like electronic medical records, which system
designers need to better tailor to specific conditions or scenarios. The findings revealed that the
organization's leaders had implemented robust policies and procedures to govern some
efficiencies surrounding the efficient use of health information technology.
Based on the findings, potential strategies can be applied, including providing enhanced
and continuous training on HIT and liaising with organizations such the AMIA for specialized
training (Guint et al., 2019). The following strategy would be having a planned, effective HIT

169
system design and tools tailored for specific conditions or scenarios. Increasing communication
and collaboration among the healthcare professionals and their information technology
department would help the organization efficiently use HIT.
Recommendations for Further Study
The researcher has two recommendations based on the analysis of the findings. The first
recommendation would be a study on how increasing formalized training programs could
effectively impact the efficient use of health information technology. Increasing training to
include formal training of healthcare professionals in HITs like electronic medical records will
improve useability issues and strengthen efficiency. To ensure appropriate and successful
utilization of HIT, education, and programs must be implemented considering individual
healthcare professional needs and their existing competencies (Guint et al., 2019). By addressing
specific knowledge gaps and providing ongoing support, healthcare organizations can empower
their staff to navigate digital tools efficiently (Konttila et al., 2019). Continuous training needs
assessment on staff competencies in using health information technology can be used as the
initial strategy for developing and designing educational strategies (Purnell, 2020).
The second recommendation for future study would be to explore the health and
information technology systems and tools that could be tailored to specific positions or scenarios
to help address the inefficiencies. The findings in this study revealed deep concerns by the
medical providers about the system's design which they felt hindered their ability to deliver
quality care. The challenge with the design is also partly due to the broadness and complexity of
the healthcare industry, as they stated. Health information technology has the potential to
improve quality care delivery. Challenges related to its design can affect its efficient use.
Therefore, it is essential to involve end users such as healthcare professionals, administrators,

170
and patients in its design and tools, including software development. These end users have the
knowledge and experience that could tremendously enhance the solution with the challenge
(Tang et al., 2018). By listening to the end user's perspective on system and tool design, the
designers could tailor the design and implementation to align closely with users' requirements
(Tang et al., 2018).
Reflections
This section will first discuss the personal and professional growth of the researcher.
Next, provide a detailed discussion on how the business functions in this study integrate with the
Christian worldview. The researcher will incorporate specific biblical references that illustrate
the relationship.
Personal and Professional Growth
In conducting this study, the researcher had to complete a substantial number of tasks in
the form of chapters in the research study. Upon successful completion of the preliminary tasks,
including the first defense, the researcher had to get approval from the school’s IRB, and then
following that the administration committee granted the researcher the approval to go into the
field for data collection. Initially, gaining access to a healthcare organization’s gatekeeper proved
difficult. Creswell and Poth (2018) stated that researchers must seek institutional approval before
collecting data. To begin the process, the researcher sent out letters to a few healthcare
organizations requesting permission to collect data. Several of them either did not respond or
rejected the request because their staff members were too busy with other business schedules and
could not accommodate the researcher’s request for interviews. The researcher did not give up;
instead prayed to God for help through this process. Through patience and persistence, the

171
researcher continued sending out letters. The researcher’s request was accepted by LGH
leadership, who assigned the HIM director to work on recruiting participants.
Before the director could do that, the researcher had to go through another process with
their in-house IRB to fulfill their requirements. Finally, the researcher gained full access to the
participants respecting their busy schedules. This reminds the researcher that persistence and
patience pay off. Gaining access to institutions can be difficult, and the researcher can have their
cooperation after being achieved after multiple strict confidentiality reassurances. Patience and
persistence are vital virtues in conquering the roads of qualitative research (Kapoulas & Mitic,
2012).
This long journey in the researcher’s study helped them reflect on past experiences with
information technology, system, and tools. Since the researcher comes from a corporate
background where they participated in system conversions or upgrades needed for the continuous
efficient performance of financial transactions and analysis, conducting this study in a healthcare
setting enriched the researcher’s knowledge of what elements are critical in adopting and
implementing information technology. It became clear that training is essential in ensuring the
efficient adoption, implementation, and useability of HIT for continuous improvements leading
to the provision of quality products and services in healthcare.
Biblical Perspective
The findings in this study are in accordance with the biblical perspective. Health
information technology is one of God’s creations used by human beings to coordinate and
deliver quality care. Then God blessed them, and God said to them, “Be fruitful and multiply; fill
the earth and subdue it; have dominion over the fish of the sea, over the birds of the air, and over
every living thing that moves on the earth” (Genesis 1:28, NKJV). Humans are commanded to

172
till and subdue the earth (Keller, 2014). As we cultivators, we change the land and make it
fruitful, meaning we are called upon to engage in continuous improvement, which adds value to
production processes, outputs, and whatever work we are engaged in to improve business and
contribute to efficiencies that will lead to increased revenue in efforts towards the advancement
of God’s purpose for business on earth.
The findings revealed two major issues impacting the efficient management of health
information technology. The healthcare professionals needed adequate training and there were
issues with the design of the system and tools needed for HIT to implement coordinated care
delivery. The findings further revealed that the healthcare organization used policies and
procedures to govern the efficient use of HIT. A biblical understanding of the efficient
management of health information technology as a system to complete God’s work of
coordinating quality care delivery energies our desire to create value from the resources available
to us in which training plays a significant part.
For the moment, all discipline seems painful rather than pleasant, but later it yields the
peaceful fruit of righteousness to those who have been trained by it. Therefore, lift your
drooping hands and strengthen your weak knees, and make straight paths for your feet, so
that what is lame may not be put out of joint but rather be healed. (Hebrews 12:11-13,
ESV)
So, I exhort the elders among you, as a fellow elder and a witness of the sufferings of
Christ, as well as a partaker in the glory that is going to be revealed: shepherd the flock of
God that is among you, exercising oversight, not under compulsion, but willingly, as God
would have you; not for shameful gain, but eagerly; not domineering over those in your
charge, but being examples to the flock. And when the chief Shepherd appears, you will

173
receive the unfading crown of glory. Likewise, you who are younger be subject to the
elders. Clothe yourselves, all of you, with humility toward one another, for “God opposes
the proud but gives grace to the humble. (Peter 5:1-5, ESV)
The design of the systems and tools are also one of God’s creations. The improvement of
the design of systems and tools is needed to utilize HIT efficiently for quality care improvement
and output. As Christians, this finding reminds us that we need to continue to follow God’s
principle of continuous, planning, cultivation and applying various techniques which create
quality in efficient management of health information technology and add value to our
productive endeavors.
But when the goodness and loving kindness of God our Savior appeared, he saved us, not
because of works done by us in righteousness, but according to his own mercy, by the
washing of regeneration and renewal of the Holy Spirit, whom he poured out on us richly
through Jesus Christ our Savior, so that being justified by his grace we might become
heirs according to the hope of eternal life. The saying is trustworthy, and I want you to
insist on these things, so that those who have believed in God may be careful to devote
themselves to good works. These things are excellent and profitable for people. (Titus
3:48, ESV)
The LORD said to Moses,
See, I have called by name Bezalel the son of Uri, son of Hur, of the tribe of Judah, and I
have filled him with the Spirit of God, with ability and intelligence, with knowledge and
all craftsmanship, to devise artistic designs, to work in gold, silver, and bronze, in cutting
stones for setting, and in carving wood, to work in every craft. And behold, I have
appointed with him Oholiab, the son of Ahisamach, of the tribe of Dan. And I have given

174
to all able men ability, that they may make all that I have commanded you. (Exodus 31:1-
6, ESV)
The utilization of policies and procedures as revealed in the findings are to govern the
efficient management of health information technology in accordance with the biblical
implications. The work healthcare provides perform using HIT is a service to God and thy
neighbor. Ensuring proficient management through the implementation of policies and
procedures for employees and stakeholders is a means of fulfilling the goals of business for the
benefit of all mankind. “Let every person be subject to the governing authorities. For there is no
authority except from God, and those that exist have been instituted by God” (Roman’s 13:1,
ESV). “For in him all things were created: things in heaven and on earth, visible and invisible,
whether thrones or powers or rulers or authorities; all things have been created through him and
for him” (Colossians 1:16, ESV). “Let the wise hear and increase in learning, and the one who
understands obtain guidance” (Proverbs 1:5, ESV).
Summary of Reflections
The study focused on the inefficient management of health information technology and
what healthcare organizations do to address this issue. The research also added value to the
researcher’s personal and professional growth and spiritual significance in business research. The
researcher gained more insight into health information technology, issues surrounding its
management inefficiencies, and the methods used to address them. On a personal note, with
persistence and patience, the researcher learned how to gain access to the gatekeeper before
resuming collecting data (Creswell & Poth, 2018).
The biblical perspective demonstrates and reinforces the significance of business research
to advance God’s purpose for business on earth. Faith is the belief in God based on spirituality. It

175
is confidence in the truth one believes, hopes, and embraces. Business research is a calling from
God. This secular notion of faith capital embodies an energizing attitude that drives a group
toward its goal and nurtures the realization of reform goals and transformative organizational
learning. As Christians, we follow a similar method: We often ask questions about life and
destiny. We research and draw conclusions based on the research findings and test our
experiences against our conclusions (Busenitz & Lichtenstein, 2019).
Summary of Section 3
This section first provided an overview of the study. Then it focused on discussing the
presentation of findings, how the study could be applied to professional practice, the
recommendation for further study, and the reflections. The analysis of the data the researcher
obtained from the telephone interviews with LGH participants confirmed that there needed to be
a solution to manage HIT efficiently. The significant factors that contributed to the inefficiencies
were the need for adequate training on the system and the design of the systems and tools.
However, this healthcare organization has implemented robust policies and procedures to govern
the efficient management of health information technology. Besides the training and system
design, the findings revealed other minor issues related to the system slowness or downtime,
copy and paste features that resulted in errors due to lack of attention to detail, and other coding
errors. The findings overwhelmingly confirmed that inefficiencies can impact the organization's
business reputation based on external organization ratings.
Based on the findings, the researcher recommended a few strategies that could be
implemented to improve the inefficiencies. They included providing enhanced and continuous
training to healthcare professionals, ensuring the planned, effective design of HIT tools and
systems that can help accelerate efficient use, and increasing collaboration and communication

176
amongst healthcare professionals to enhance knowledge sharing. Based on the analysis and
conclusion of the findings, the researcher recommended two studies for further research. They
were to assess how formalized training in HIT could positively impact its management
efficiencies and explore the HIT tools and systems that could be tailored to the specific position
or scenario through the end user's involvement. This study added value to the researcher's
personal and professional growth by better understanding why the inefficiencies in HIT occur
within a healthcare organization. The research process in this study enlightened and increased the
researcher's perspective on why persistence and patience are key to success, specifically in
gaining access to the gatekeeper to collect data. The biblical perspective demonstrated and
reinforced the importance of continuously improving upon God's creations like information
technology, to ensure that it is managed efficiently for quality improvement and output
improvement, leading to the advancement of God's purpose for business on earth.
Summary and Study Conclusions
Health information technology can improve the provision of quality care delivery. If not
designed, implemented, and managed efficiently, it can impact the safety and quality of care
delivery, potentially negatively impacting the organization’s business (Sittig et al., 2020). The
general purpose of this single case study was to explore current management issues surrounding
health information technology in healthcare organizations. The specific purpose was to explore
potential management issues with health information technology management in Lancaster,
Pennsylvania, with Lancaster General Hospital. To understand the problem, the researcher
crafted the following research questions:
RQ1: How has the mismanagement of health information technology within healthcare
organizations led to medical errors, which resulted in the disruption of healthcare delivery?

