


Background and Historical Context
Healthcare is the fastest growing industry in the United States and globally (Bureau of
Labor Statistics, 2022). Economists forecast that as the population grows and life expectancy
increases, the healthcare sector will continue expanding to meet consumer needs domestically
and globally (Bureau of Labor Statistics, 2022). Aging populations will lead to increased demand
for healthcare services, which is a key factor that will contribute to growth in the sector
(Swanson, 2022).
In 2021, the global healthcare industry was worth $12 trillion. In the United States, the
healthcare sector reached $4.1 trillion, as reported by the American Medical Association (2023).
The spending accounted for 20% of the U.S. GDP in this time period. Healthcare is a complex
massive industry that accounts for 20% of the United States' gross domestic product in 2020
(Insider intelligence, 2023). Industry projections suggest that the healthcare market will reach
$6.2 trillion by 2028 (American Medical Association, 2023; Gebreyes et al., 2021).
Healthcare is economically important to the U.S., given the annual wages for clinician
occupations (surgeons, physicians, or registered nurses) exceed $75,000, which is higher than
the median annual wage of $45,760 for all occupations in the economy (Bureau of Labor
Statistics, 2021, 2022). Consideration of the supply of healthcare professionals to fill the jobs is
a gap that needs to be addressed by chief executives. Leading organizational change for
sustainable growth and vitality is critical, especially during time of tumultuous business volatility,
economic uncertainties, and unprecedented complexities (Austin & Gilmore, 1993; Chadi, 2009;
Kotter et al., 2021). At a time when the availability of the labor pool to fill openings is widening,
organizational leadership is confronted with creating alignment of the company’s strengths in
ways that deescalate the relevance of a system’s weaknesses (Drucker, 1993).
According to the Bureau of Labor Statistics (2022), employment in the healthcare sector
will grow by 16% between 2020 and 2030. The growth projection will add 2.7 million new jobs,

making healthcare the fastest growing occupation than the average of all occupations combined
(Insider Intelligence, 2023). Simultaneously, staff shortages remain a top priority on the list of
concerns for chief executives, combined with operational challenges requiring change while
striving to maintain profitable growth to support the organization’s mission. Between 2000 and
2030 the U.S. confronts a shortage of clinicians: up to 122,000 physicians, 500,000 registered
nurses, and more doctors near retirement age of 65 in the next decade (Bureau of Labor
Statistics, 2022).
A stabilized workforce is a primary focus of hospital chief executive officers (CEOs), with
94% citing staffing shortages and the lack of RNs as the predominant concern (Advisory Board,
2022). The American Hospital Association (2021) reported approximately 1.7 million people
resigned from their healthcare positions which is an estimated loss of 20% of its workforce and
30% of nurses (AHA, 2021; Gazelle, 2022). Few industries have experienced the magnitude of
a mass exodus of workers as healthcare which is important because of the industry’s impact on
occupations and the health of the nation. Employment shortages in the field remain at 80,000
jobs, a figure that has persisted since February 2020 (AHA, 2021).
Problem Background
As significant and problematic general turnover is in the healthcare workforce,
executivelevel resignations pose an even more serious threat to the industry. Research by
Challenger, Gray & Christmas, Inc. (2022) indicates that 97 hospital CEOs left their roles in
2022. CEO turnover increased by 53% in the largest publicly traded corporations between 1995
and 2001 as CEO tenure declined from 9.7 years to 7.3 years during the same period of time
(Lucier et al., 2002).
Furthermore, succession planning appears to be neglected in the industry. Studies
indicate that 79% of U.S. hospitals do not routinely conduct succession planning for senior-level
positions (ACHE, 2011b; Garman & Tyler, 2007) and 25% of hospitals took 6 months to 1 year to

replace a departed CEO (ACHE, 2011a; Khaliq et al., 2006). In addition, the study illuminates
the effect of CEO turnover on hospital administration when the position is vacant. Most
significantly, more than 5% needed more than a year to name a CEO which served as a trigger
event for other key staff members' consideration of leaving the organization (Khaliq et al., 2006).
Challenger, Gray & Christmas, Inc. (2022) found that CEO turnover specifically in large hospital
systems increased from 18 in 2018 to 32 in 2022 (see Figure 1).
Figure 1
Large Hospital Executive Turnover: 2018-2022
A 2012 study of internally promoted and externally placed CEOs show the majority felt
the board of directors should have more involvement in the transition process. Even when an
abandoned CEO position is filled, only one in five CEOs hired externally are evaluated as a high
performer by the end of their first year of employment, and close to half of the newly hired
executives leave within the first 18 months of being hired (Shen & Cannella, 2002). Challenger,
Gray & Christmas, Inc. (2022) reported that the leading reasons for CEO departures include
retirements, pursuit of new opportunities, transition into other C-suite roles, and step-downs (see
Figure 2). Other research has revealed that the intense pressure CEOs experience around the
clock, their inability to take time off from work, and renewed personal clarity since the pandemic
also factor into CEOs’ decisions to leave (Advisory Board, 2022). These various pressures have
reduced the median time they spend in position, increased the rate of chief executive exits, and
shifted the reasons for their departures (Probert, 2015).
Figure 2
Reasons for Healthcare Executive Departure

Additionally, leader engagement declines are problematic among those CEOs who stay
in their roles. Research by the Advisory Board (Johnson, 2016) found that over the period from
2012 to 2014, engagement declined 3.9% for managers, 4.2% for directors, and 4.4%
executives. In comparison, engagement declined for frontline staff only 0.4%, indicating that
leader engagement is declining 10 times more than that of frontline staff. Lack of executive team
engagement could undermine their ability to execute the strategy on a daily basis and translate
action into purpose for frontline staff, ultimately leading to organizational failure (Advisory Board,
2022).
Researchers have acknowledged the significant effect that CEOs have on their
organizations (Finkelstein et al., 2009; Hutzschenreuter et al., 2012). Leadership
disengagement and instability has negative consequences for their organizations and for
national health (ACHE, 2022a; Venkataramani et al., 2020). Empirical evidence of the impact of
hospital CEO turnover is limited with perilous implications for impacted systems (Khaliq et al.,
2006). The powerful nationwide impact of healthcare executive turnover and disengagement
indicates the need to examine the phenomenon of transitions and what could be done to
improve their success.
Purpose Statement
The purpose of this study is to identify strategies and organizational practices for CEO
transitions at large hospital systems during times of significant multidimensional change. In this
study, a large hospital system is defined as a multi-hospital, multi-region institution that employs
more than 25,000 individuals. Multidimensional change is defined as volatile, complex,
uncertain, and ambiguous conditions that ignite social, economic, and workforce shifts within
and outside the organization. More broadly, the study’s aim is to offer insights to organizations
that wish to improve the success of CEO transitions, especially during times of multidimensional
change.

Research Questions
The following research questions were addressed in this study:
• RQ1: What are the most important organizational practices for CEO transition in
large hospital systems during times of multidimensional change?
• RQ2: Is there a broader framework for CEO transition in large hospital systems
during times of multidimensional change that could be arrived at by further
reduction of the data?
Theoretical Framework of Constructivist and Appreciative Inquiry
Leadership is a social construct comprised of multiple models and paradigms (Swanmick
& McKimm, 2011). Executive transitions are concurrently driven by and bound by the
organizational context in which it takes place (Royer & Latz, 2015). In other words, executives in
transition need to be cognizant of the organizational history, context, values and mission while
successfully navigating change. Boggs (2011) suggests the criticality of considering the myriad
ways executive transitions influence the overall health and future sustainability of an
organization (Bolman & Deal, 2013; 2017).
Theoretical frameworks related to this study are constructivist principles and appreciative
inquiry. Constructivist theory principles relate to this study based on the notion that it suggests
that what is known about an organization and its destiny is interwoven with multiple perceptions,
realities and shared understandings by its members (Burr, 2015; Gergen, 1999; “Social
Constructionism,” 2013). Mead (1930) created the concept of “symbolic interactionism,” which
postulates that people construct their identities and the identities of others through their daily
encounters with each other. In the seminal work, Mind, Self, and Society, Mead (1930) outlines
the foundational aspects of the sociological construct of social constructionism by positing that
the self is created through people’s social interactions. Berger and Luckmann (1966) advanced
and formally hypothesized the introduction of social constructionism into the sociological

vocabulary. In the pivotal seminal writing, The Social Construction of Reality, Berger and
Luckmann (1966) contend that social phenomena are created and sustained through three
processes: externalization, objectivation and internalization. People’s thoughts on the world are
externalized through writing or fashioning a story about an idea which creates a practice or
artifacts. As other people adopt the idea, engage in sharing the story, or embrace the artifacts,
the idea becomes an objective truth. Objectivation of the idea turns it in to an objective truth. As
it is internalized in the consciousness of society, future generation’s adoption of the idea,
practice or artifact occurs based on its preexistence (Berger & Luckman, 1966; Burr, 2015;
Schneider, 2018). Berger and Luckmann (1966) theorizes how social practices are constructed
by people and become artifacts of factual truths. Flaskas (1993) asserts that social
constructionism provides a comprehensive framework for social behavior and the constructed
worlds that people reside (Gergen & Gergen, 2012).
Social constructionist theorizes that people and their individual differences are created or
constructed through social processes (e.g., political, religious, and economic) rather than an
innate quality within the individual (Gergen, 1999). A primary differentiation of social
constructionism is that knowledge is sustained by the existence of social processes (Young &
Collin, 2004). Gasper (1999) contends that social constructionism is knowledge that is derived
as a product of social practices and institutions that are manifested through relevant interactions
between social groups. The principle ideates that a social system creates or determines its own
reality (Cooperrider et al., 2003). No one reality or truth exists. Instead, truth is grounded in the
multiple and contextually determined realities of peoples’ perceptions, dialogues, and shared
understandings (Cooperrider et al., 2003).
Social constructionism theory heavily influenced the creation of the Appreciative Inquiry
framework. The intersection of social constructionism and appreciative inquiry inherently serves
as the theoretical framework that foundationally operates from the principle of positive context.

Positive context operates from a premise that “people control their destiny by envisioning what
they want and developing actions to move toward it” (Cooperrider et al., 2003 p. 13).
Further, the constructionist principle implies that human knowledge organizational
change is implicit with the first questions asked, which becomes the fodder for how the future is
conceived and constructed (Cooperrider et al., 2003; Gergen, 1999). Cooperrider et al. (2003)
argue that human knowledge and organizational destiny are interwoven constructs. Executives’
effectiveness is contingent on organizations being understood through human constructs. In
other words, being “adept in the art of reading, understanding, and analyzing organizations as
living, human constructions” (Cooperrider et al., 2003, p. 8).
Organizational leadership is tasked with creating an alignment of strengths in ways that
make a system’s weaknesses irrelevant (Drucker, 1993). Organizations that are defined by rote
habitual styles of thought constrain imagination for the future and define the way the
organization operates. Along these lines, change requires sizeable volumes of positivity of social
connection of members in co-creating hope and mutual inspiration. Hence, organizations as
human constructions are primarily affirmative systems which respond to positivity in knowledge
and thoughts (Cooperrider & Whitney, 1999; Cooperrider et al., 2003). Bushe and Coetzer
(1995) contend that more positive questions are used in a change endeavor create lasting and
effective outcomes. As such, the premise is people move toward their inquiries.
The second framework of this study examines executive transitions through the prism of
appreciative inquiry. Appreciative Inquiry methodology is based on the principle that positive
organizational futures can be attained through people’s collective affirmative involvement
(Cooperrider et al., 2008). The theoretical framework of appreciative inquiry is rooted in social
constructionist that links ways of studying and understanding organizations (Royer & Latz,
2015). Appreciative inquiry is a philosophical model of change devised as a methodology that
applies a set of tools that can be instrumental in facilitating executive transitions. The framework

establishes a way of being for organizations experiencing multidimensional change and
executive transitions (Keefe & Pesut, 2004; Simons & Havert, 2012).
Principles of appreciative inquiry have epistemological grounding in constructionism.
Crotty (1998) postulates, “In the constructionist view, as the word suggests, meaning is not
discovered but constructed” (p. 42). Cockell and McArthur-Blair (2012) assert that the
epistemological approach of appreciative inquiry solidifies approaches to bring people together
as learners in collegial communities where cultures are constructed based on common realities
and shared meanings. In studying practices that increase the success of executive transitions,
appreciative inquiry offers a theoretical framework that Cooperrider and Whitney (1999)
explained as “Rather than explaining yesterday’s world, it articulates tomorrow’s possibilities” (p.
15).
Social knowledge and organizational change intersect in the constructionist principle.
Appreciative inquiry framework offers a cadre of tools and techniques that inform how an
organization moves toward a collective destiny through four prisms: discovery, dream, design,
and destiny, referred to as the four D’s (Cooperrider et al., 2008).
Appreciative inquiry is an iterative cycle that flows through the 4Ds:
● Discovery: this stage entails introspection and discussion about what is in an
organization. Participants delve into the organization to unearth and value the
exceptional best of what gives life to the organization’s existence. During the
discovery stage all stakeholders are engaged in articulating the strengths and
organizational practices to result in uncovering the best of the past and that of the
future.
● Dream: solicits participants to consider the possibilities for the organization to
change by crystalizing the vision in results orientation from discovery.

● Design: participants migrate ideas from the dream phase to construct practical
structures to bring reality to the possibilities in articulating the organization design
that magnifies the positive.
● Destiny: creation of a vision that inspires the implementation of the designs into the
constructs of the organization. In this stage the outcome is to strengthen the
affirmative capabilities of the organization in a manner that cultivates optimism and
positive change toward attaining performance goals (Barrett, 2020).
Appreciative inquiry four D principles are an iterative process with encouragement to
continue the process to achieve improvements (Cooperrider & Whitney, 1999), illustrated in
Figure 3.
Figure 3
Appreciative Inquiry Four-D Model
Royer and Latz (2015) research on appreciative inquiry in the context of executive
transitions suggests there is a significant role that is addressed by understanding the needs of
the varied participants during the transition process begins with discovery. First, participants of
the transition are exiting chief executives who have a vast array of institutional knowledge to
share through the appreciative inquiry methodology. In the discovery stage the chief executive
transitioning into the organization gains insights and appreciation of the organizational context to
develop the organizational culture. Third, using appreciative inquiry assuages uncertainty of the
members of the organization and chief through the duration of the transition (Bennis, 2002;
Bolman & Deal, 2013). Discovery fosters an approach that encourages full participation of all
organizational members to establish an atmosphere of trust (Yoder, 2004). Transitions built on
trust are critical elements in transferring knowledge to a next generation of leaders (Lustig &
Ringland, 2010; Mather & Hess, 2013; Royer & Latz, 2015).

The nature and elements of the theoretical framework of appreciative inquiry discover,
dream, design, and destiny allay cooperative constructs future while at the same time
encouraging individual participation. The phenomena of executive transitions are inextricably
linked with organizational effectiveness and leadership effectiveness. In the context of chief
executive transitions, a unique inflection point provides an opportunity for organizational
selfanalysis and growth, particularly at times of multidimensionality when the organization
requires repositioning for its future needs (Bolman & Deal, 2017; Bushe & Coetzer, 1995;
Cooperrider et al., 2008).
Significance of the Study
This study is anticipated to produce needed insights about how to effectively navigate
CEO transitions. An examination of CEO transitions during times of multidimensional change
resembles some facets of organizational and culture change that occur during merger and
acquisition (M&A) transactions. Fernandes et al. (2010) research suggests that M&A’s duality
presents opportunities and challenges for executive teams who are responsible for the success
of the transaction and leading their organizations during times of ambiguous uncertainty.
Activities before, during and after M&A deals generate significant change that create complex
situations that chief executives must navigate people through the transition.
Research highlights the reality that the majority of mergers do not live up to expectations
and many fail entirely (Fernandes et al., 2010). Getting the human capital aspects of the
transition right increases the likelihood that the deal will meet its objectives (Fernandes et al.,
2010). Lessons to learn from mergers and acquisition transactions are applicable to an
executive transitioning during multidimensional change. Research indicates that people
experience a variety of workplace uncertainty throughout the merger and acquisition transaction
(see Figure 4). Behaviors people experience reflect the challenges and pressures along the
continuum of the deal. For that reason, some researchers and practitioners compare the change

process to that of the grief process (see Figure 5). Knowles and Vickers (2010) highlight
mitigation actions instrumental to chief executives’ role as champions in leading successfully
transitions. Paramount to the mitigation actions is the mind shift required by chief executives to
embrace a vision for success of the organization in the future over inwardly focusing on
themselves.
Figure 4
Typical Behaviors Experienced During M&A Transitions
Researchers’ examination of organizational change as a result of transitions juxtaposes
the phenomenon against a backdrop of Kübler-Ross’ (1969) change curve model (Leybourne,
2016). The model outlines behavioral motivations or performance people experience as they
traverse through a range of stages. Surprise about an experience leads to denial of the
existence of the situation that manifests into frustration. A period when people experience low
energy or minimal motivation is described as the valley of despair. As time progress from the
initiation of the change, people move to experiment, adapting and learning how to work with new
conditions and ultimately to integrate the change (see Figure 5).
Figure 5
Kübler-Ross Change Curve Model: Valley of Despair
Fernandes (2010) amplifies unintended consequences of leadership transitions during a
merger and acquisition deals that have significance to this study. For example, a shift in power,
leaders’ opportunity to influence is downgraded and decisions made by the new boss are among
the triggers that signal change and send tremors of uncertainty across the organization
(Fernandes et al., 2010). Similar to merger and acquisition transactions, CEO transitions raise
uncertainties that impact business operations as speculation and opining replace performance

productivity, which reinforces the stance that leadership transitions are stressful and full of
uncertainties for members of an organization (Fernandes, 2010).
Leadership is the essential element to successful implementation of organizational
change (W. Burke, 2017, 2008; Ford et al., 2021; Kotter, 1996; Kotter & Schlesinger, 2008;
Nadler & Tushman, 1990). Healthcare is myriad with complexity built on systems that involve
large numbers of people (Swanmick & McKimm, 2011). Leaders capable of generating
constructive organizational change to navigate between the group’s ability to unlock imaginative
competence is essential. Healthcare executives report that many of the strategic changes they
attempt to advance within their organizations fail (Johnson, 2017).
Data from the Advisory Board (Johnson, 2017) data suggests that two out of every three
change imperatives in healthcare fail largely attributed to the majority of employees that do not
change the way they work to reflect the strategic initiatives. When these transitions are done
well, organizations prepare a new leader with a change agenda, and the leader is better
equipped to turn it into power dynamics on how the culture influences a strategy shift or what
cultural changes will be necessary to support the strategic imperatives (Ciampa, 2016; Dotlich,
2016; Watkins, 2003). Further, successful transition pathways establish foundations for
productive relationships between key stakeholders, the CEO, and board members (Ciampa,
2016).
Assumptions
The primary assumption of the present study is that the participants have relevant
perspectives related to the characteristics of successful CEO transition in large hospital
systems, especially during times of multidimensional change. Additionally, the researcher
assumed that study participants would freely offer their viewpoints in the various stages of
research. Consistent with Pepperdine University Institutional Review Board guidelines,

participants are assumed to have given informed consent and that appropriate measures were
applied to protect their privacy and wellbeing.
Limitations
This study is limited to 30 individuals who are parties to CEO transition in large hospital
systems. The opinions of these participants should not be considered to be generalizable to all
CEO transitions, even those within large hospital systems. Moreover, to reduce any bias from
any one viewpoint, care was taken to recruit a diverse sample in terms of tenure, ethnicities, and
geography. Furthermore, the multidimensional change affecting most organizations during the
study timeframe was the coronavirus pandemic. Future experiences of multidimensional change
facing the organization may have different impacts, requiring different elements to support
successful CEO transition. The present study also was conducted within the context of the
Pepperdine University Institutional Review Board (see Appendix A), which imposes restrictions
on the design and execution of the study.
Definition of Terms
Academic Medical Center: a tertiary care hospital that is organizationally and
administratively integrated academically with a university’s medical school (Joint Commission
International, 2022). Academic hospitals provide the principal site to educate postgraduate
medical trainees and medical students. Under approved protocols involving human subjects,
academic medical centers conduct academic, commercial or medical human subjects’ research.
Appreciative inquiry: a conceptual framework used to construct change management
through joint exploration for the best in people, the organization and the environment that
surrounds them which is achieved by systematic discovery to identify what works well, analysis
why it works well and then applying focus on doing more of what is working. Used for
organizational analysis, managerial problem solving and as a change management approach
(Cooperrider et al., 2008)

Board of directors, board of trustees: independent members with fiduciary responsibility
to provide governance, oversight of strategy, evaluate the financial performance, hiring and
termination decisions of chief executive officer or the executive cabinet.
Chief executive roles: chief executive officer (CEO), chief operating officer (COO), chief
human resources officer (CHRO), chief financial officer (CFO); chief medical officer (CMO), chief
information officer (CIO), chief nurse executive (CNE).
Chief executive transition: the process of a chief executive officer leaving the
organization to be replaced by a new chief executive officer (Allison, 2002; Wiggins, 2019).
Culture: a collective set of shared attitudes, goals, behaviors and values that shape
hospitals outcomes and future growth (Schein, 2010).
Large hospital system: a multi-hospital, multi-region institution that employs more than
20,000 individuals with annual net revenue in excess of $5 billion (American Hospital
Association, 2021).
Multidimensional change: volatile, complex, uncertain, and ambiguous conditions that
ignite social, economic, and workforce shifts within and outside the organization (Nelson & Pilot,
2015).
Multidimensionality: is defined as “the quality of a construct that cannot be adequately
described by measuring a single trait or attribute” (“Multidimensionality,” 2023).
Organizational culture: the beliefs, values, attitudes, and actions of the people in the
organization and how these factors influence the member’s behavior (Schein, 2010).
Registered nurse (RN): a clinically trained nurse who has matriculated and graduated
from a formal program of nursing with a degree and has attained licensing from the governing
authority of the state (American Nurses Association, 2023).
Social constructionism: a theory that knowledge is existential to the reality that people
give to various aspects of the world through social agreement (Gergen, 1999).

Succession management and planning: a systematic framework to identify, select, and
develop key individuals to plan for the ascension into critical roles that aids the organization to
be prepared for the future. An endeavor to ensure leadership continuity, protect intellectual
capital and preserve institutional knowledge for the future viability of an organization (Hassan &
Nasibollah, 2016).
Teaching hospital: a hospital that improves healthcare through learning and research in
partnership with nursing schools, medical schools, research centers and education programs
(Duffy, 2011; Iglehart, 1993; Ludmerer, 1983; Neely & McInturff, 1998).
Tripartite mission: defines the role of academic health centers to educate health care
workforce, conduct clinical and biomedical research that is innovative, and provide high caliber
care to patients (AHA, 2022; Aron, 2023; Blumenthal et al., 1997; Grover et al., 2014;
Smitherman et al., 2019).
Chapter Summary
Healthcare is the fastest growing industry in the United States and globally (Bureau of
Labor Statistics, 2022). Economists forecast that as the population grows and life expectancy
increases, the healthcare sector will continue expanding to meet consumer needs domestically
and globally (Bureau of Labor Statistics, 2022). Population aging and the emergence of global
pandemics has substantially increased the demand for healthcare services and has created
volatile, complex, uncertain, and ambiguous conditions that ignite social, economic, and
workforce shifts within and outside the organization (Billiones, 2019). While these factors require
growth and agility within healthcare organizations, high turnover in the healthcare workforce
threatens these organizations’ ability to effectively fulfill their mission.
Healthcare organizations face significant challenges that will require executive attention
to break down existing organizational barriers to achieve different outcomes (Swanson, 2022).
The high rate of chief executive turnover within large hospital systems poses particularly

significant threats to the industry and national health (AHA, 2021). As discussed in this chapter,
criticality of considering the myriad ways executive transitions influence the overall health and
future sustainability of an organization is an important phenomenon (Boggs. 2011; Bolman &
Deal, 2013, 2017). Therefore, this study identified strategies deemed as organizational practices
for chief executive officer transitions at large hospital systems during times of significant
multidimensional change.
Theoretical frameworks related to this study are constructivist principles and appreciative
inquiry. Swanwick and McKimm (2011) expound on the importance of clinical leadership in
healthcare. Each framework contributes to the significance of the study in a cogent approach to
addressing transitions of CEOs during multidimensionality. Multidimensional change in business
is a constant and is a relevant topic that appears to be a dynamic for chief executives, board of
directors and CEOs whether in large health systems, academic medicine teaching hospitals and
in general. Associated with multidimensionality factors, CEO transitions are on the rise as time
in position is declining. Therefore, an examination of the strategies deemed successful has
significance to identify the most important practices for CEO transition in large hospital systems
during times of multidimensional change. In addition, exploring if there is a broader framework
for CEO transition in large hospital systems during times of multidimensional change brings
significance to the study given the critical role of healthcare in the U.S. and globally.
This study is anticipated to produce needed insights about how to effectively navigate
CEO transitions. An examination of CEO transitions during times of multidimensional change
resembles some facets of organizational and culture change that occur during merger and
acquisition transactions. Fernandes et al. (2010) research suggests that merger and
acquisition’s duality presents opportunities and challenges for executive teams who are
responsible for the success of the transaction and leading their organizations during times of
ambiguous uncertainty. Chief executive officer transitions and post merger and acquisition deal

activities have symbiotic resemblance as they both generate significant change that create
complexity for CEOs, chief executives, board of directors and members’ of the organization to
navigate people through the transition.
This chapter provided an introduction to the present study, including a discussion of the
problem background and presentation of the study purpose and research questions. A
discussion of the theoretical frameworks of social constructionism and appreciative inquiry were
outlined. The study’s significance, assumptions, and limitations were acknowledged. Finally, key
terms were defined.
Chapter 2: Literature Review
The purpose of this study is to improve the success of CEO transitions in large hospital
systems, especially during times of multidimensional change. This chapter provides a review of
germane literature. Studies on large hospital systems are examined first, including a discussion
of the history of these systems, and categorizations of institutions. Industry trends and threats
are reviewed, and a discussion of leadership cultures and trends within healthcare is provided.
Research on chief executive transition is outlined next, including a history of the study and
practice of CEO transition, as well as a discussion of the process and roles in the transition.
Success and failure rates of executive transition are reviewed and consideration is given to the
effect of executives transitions and what factors contribute to transition outcomes. Special
considerations for executive transition in hospital systems are then outlined. The effect of
multidimensional change on executive transition in hospital systems is then discussed. The
present chapter concludes with a synthesis of the literature. The chapter outline is diagrammed
in Figure 6.

Figure 6
Large Hospital Systems
The present study focuses on the healthcare industry and specifically focuses on
teaching hospitals associated with universities or academic medical centers. In the U.S., there
are 5,534 registered hospitals (American Hospital Association [AHA], 2022). The sector of the
healthcare industry is comprised of several types of institutions, including teaching hospitals,
academic medical centers, large hospitals, and large academic hospital systems.
Teaching hospitals are established in various forms (see Figure 7) and are affiliated with
universities, colleges, medical schools, or nursing schools and have been the cornerstone of
healthcare delivery for over a century (Duffy, 2011; Iglehart, 1993; Ludmerer, 1983). The U.S.
has more than 1,000 teaching hospitals whose mission is to provide healthcare services to their
communities while training future healthcare providers (i.e., students, interns, fellows) under the
supervision of licensed physicians, faculty, department chairs, and other medical staff. Teaching
hospitals are a sector within the healthcare industry that operate under the auspices of
research, education and patient care in a unified and comprehensive institutional construct
(Blumenthal et al., 1997; Neely & McInturff, 1998).
Chapter 2 Outline
B of Large Health Systems
R on Chief Executive T
I Challe and CEO T
M of Success
E of Multidimensional Change on CEO T
Collectively, 2.7 million people are employed with these institutions which places the
category among the largest employers within their communities. Top teaching hospitals are
found near major cities or in densely populated states. Many are located in the northeast and
midwestern United States. A differentiation of teaching hospitals from regional hospitals is their
access to specialists and cutting-edge equipment usually not available in other communitybased
facilities.
Figure 7
Categories of Teaching Hospitals
Note. Original figure created based on Policy Priorities to Improve the Nation’s Health: From
America’s Medical Schools and Teaching Hospitals, by D. G. Kirch, 2016, AAMC
(www.aamc.org/system/files/c/2/472838-policy-priorities-improve-nations-health.pdf).
Academic medical centers are teaching hospitals with a tripartite mission of conducting
advanced research in search of medical breakthroughs, educating future clinicians, and
delivering medical care to patients. In particular, academic medical centers fulfill a crucial social
mission in caring for the uninsured and impoverished and specializing in clinical care for the
most severely ill or injured patients (AHA, 2022; Aron, 2023; Blumenthal et al., 1997; Grover et
al., 2014; Smitherman et al., 2019). Each objective has distinctive value and, collectively, the
tripartite mission has been a foundational segment of healthcare for over a century (Duffy, 2011;
50
0
150
200
250
300
100
0.0
%
10.0
%
20.0
%
30.0
%
40.0
%
50.0
%
60.0
%
70.0
80.0
%
90.0
%
100.0
%
%
Integrated
Independent
Specialty
Children's
Veteran's Affairs
Other Federal
Total
HUNDREDS
AAMC,Member Teaching Hospitals by Category, 2021 Percentage Members

Iglehart, 1993; Ludmerer, 1983; Rothman et al., 2015). Academic medical centers comprise only
6% of American hospitals (Association of American Medical Colleges [AAMC], 2021).
The AHA (2022) notes that large hospitals are distinguished by the number of patient
beds, services, locations, and employees. Large academic hospital systems have the following
characteristics: 10 or more hospitals; 700 or more patient beds; 20,000 or more employees; net
annual revenue of US$5 billion or more; inclusion in Top Hospitals lists from U.S. News and
World Report, Healthgrades, and Thomson Reuters; availability of licensed hospital beds; and
affiliation with a university or school of medicine. Large medical centers are characterized by
multiple hospital affiliations, populations of 20,000 or more employed people, number of hospital
beds greater than 1,000 and annual net revenue in excess of $5 billion.
Origins of Hospital Systems
The origins of the hospital as an institution chronicles back to 4th century Rome (Cilliers
& Retief, 2002). The inception of the hospital as an institution is closely related to religions and
wars. For example, the first military hospital appeared in Rome due to war to treat the sick and
injured soldiers (Piercey et al., 2020). During the Middle Ages, religion remained a dominant
influence in establishing hospitals, with more than 2,000 founded as monastic institutions
(Piercey et al., 2020). The institution's growth accelerated care for disease and pestilence.
Countries trendsetting occurred in Europe, Baghdad, and Damascus by admitting patients
regardless of religious affiliation, social order, or race. In France, the Hospital of the Holy Ghost
was founded in 1145 and later became one of Europe’s most important centers for training
doctors (Piercey et al., 2020). Arguably, the Hospital of the Holy Ghost was a conceptual
foundation for teaching hospitals in the future.
During the 16th century, hospitals gradually spread from Europe to North America (de
Micheli, 2005) with the primary purpose of almshouses to care for the poor. In the United States,
the first hospital was established in 1663 to care for soldiers on Manhattan Island, followed by

William Penn incorporating Pennsylvania Hospital in Philadelphia in 1713 (Piercey et al., 2020).
Conflicting recounts are in the literature on the first teaching hospital in America. Burbridge
(1957) purports that the first school of medicine in the United States opened in 1765 and later
became the first teaching hospital associated with a Pennsylvania University, established in
1874 (Kanter, 2010).
Two decades after the first teaching hospital and school of medicine affiliation, there
were many failed attempts to improve the quality of clinical instruction (Ludmerer, 1983).
Learning by doing is a principle used in scientific laboratories that was not applicable with the
clinical curriculum by medical schools. Without access to adequate hospital facilities or the
ability to appoint hospital staff to freely teach and research, medical schools lacked control to
educate future clinicians. Instead, medical schools were relegated to teaching clinicians by
illustrated lecturing of groups, rendering them as passive observers versus the practice of
learning by doing (Ludmerer, 1983).
In the early 1900’s the introduction of clerkships at Johns Hopkins School of Medicine
improved pedagogic advancements, but not holistically across other institutions given the
absence of the hospital for teaching application of medicine. The Flexner Report (Flexner, 1910)
was the seminal critique of medical training that transformed the nature and process of medical
education with the introduction of the gold standard of science-based training that notably
elevated the U.S. as a recognized global leader in medical research and medical education
(Duffy, 2011; Flexner, 1960). The importance of bi-directional crosstalk between patient, clinician
and learners creates the dialogue that incites medical discoveries and breakthroughs (Duffy,
2011). This was a significant development in the rise of the teaching hospital (Barlow, 1909;
Ludmerer, 1983). Following the Flexner Report, medical schools acquired relationships with
teaching hospitals to incorporate education and research to expand the purpose of academic
medicine. With the manifestation of teaching hospitals in the nineteenth century, homogeneity in
the quality of instruction not only increased the advancement of medicine, but also paved a
pathway for academic medicine.
While the history of hospitals is well chronicled, there is a dearth of information in the
literature about the history of academic medicine (Kanter, 2010). Following World War II, federal
subsidies helped the U.S. government build and expand hospitals (Gerber, 1995). With the
addition of modern technology and medical research, institutions grew in complexity (Piercey et
al., 2020). Academic medical centers are affiliated with universities that teach medical students
at an affiliated hospital, called a teaching hospital, to provide pedagogic experiential learning
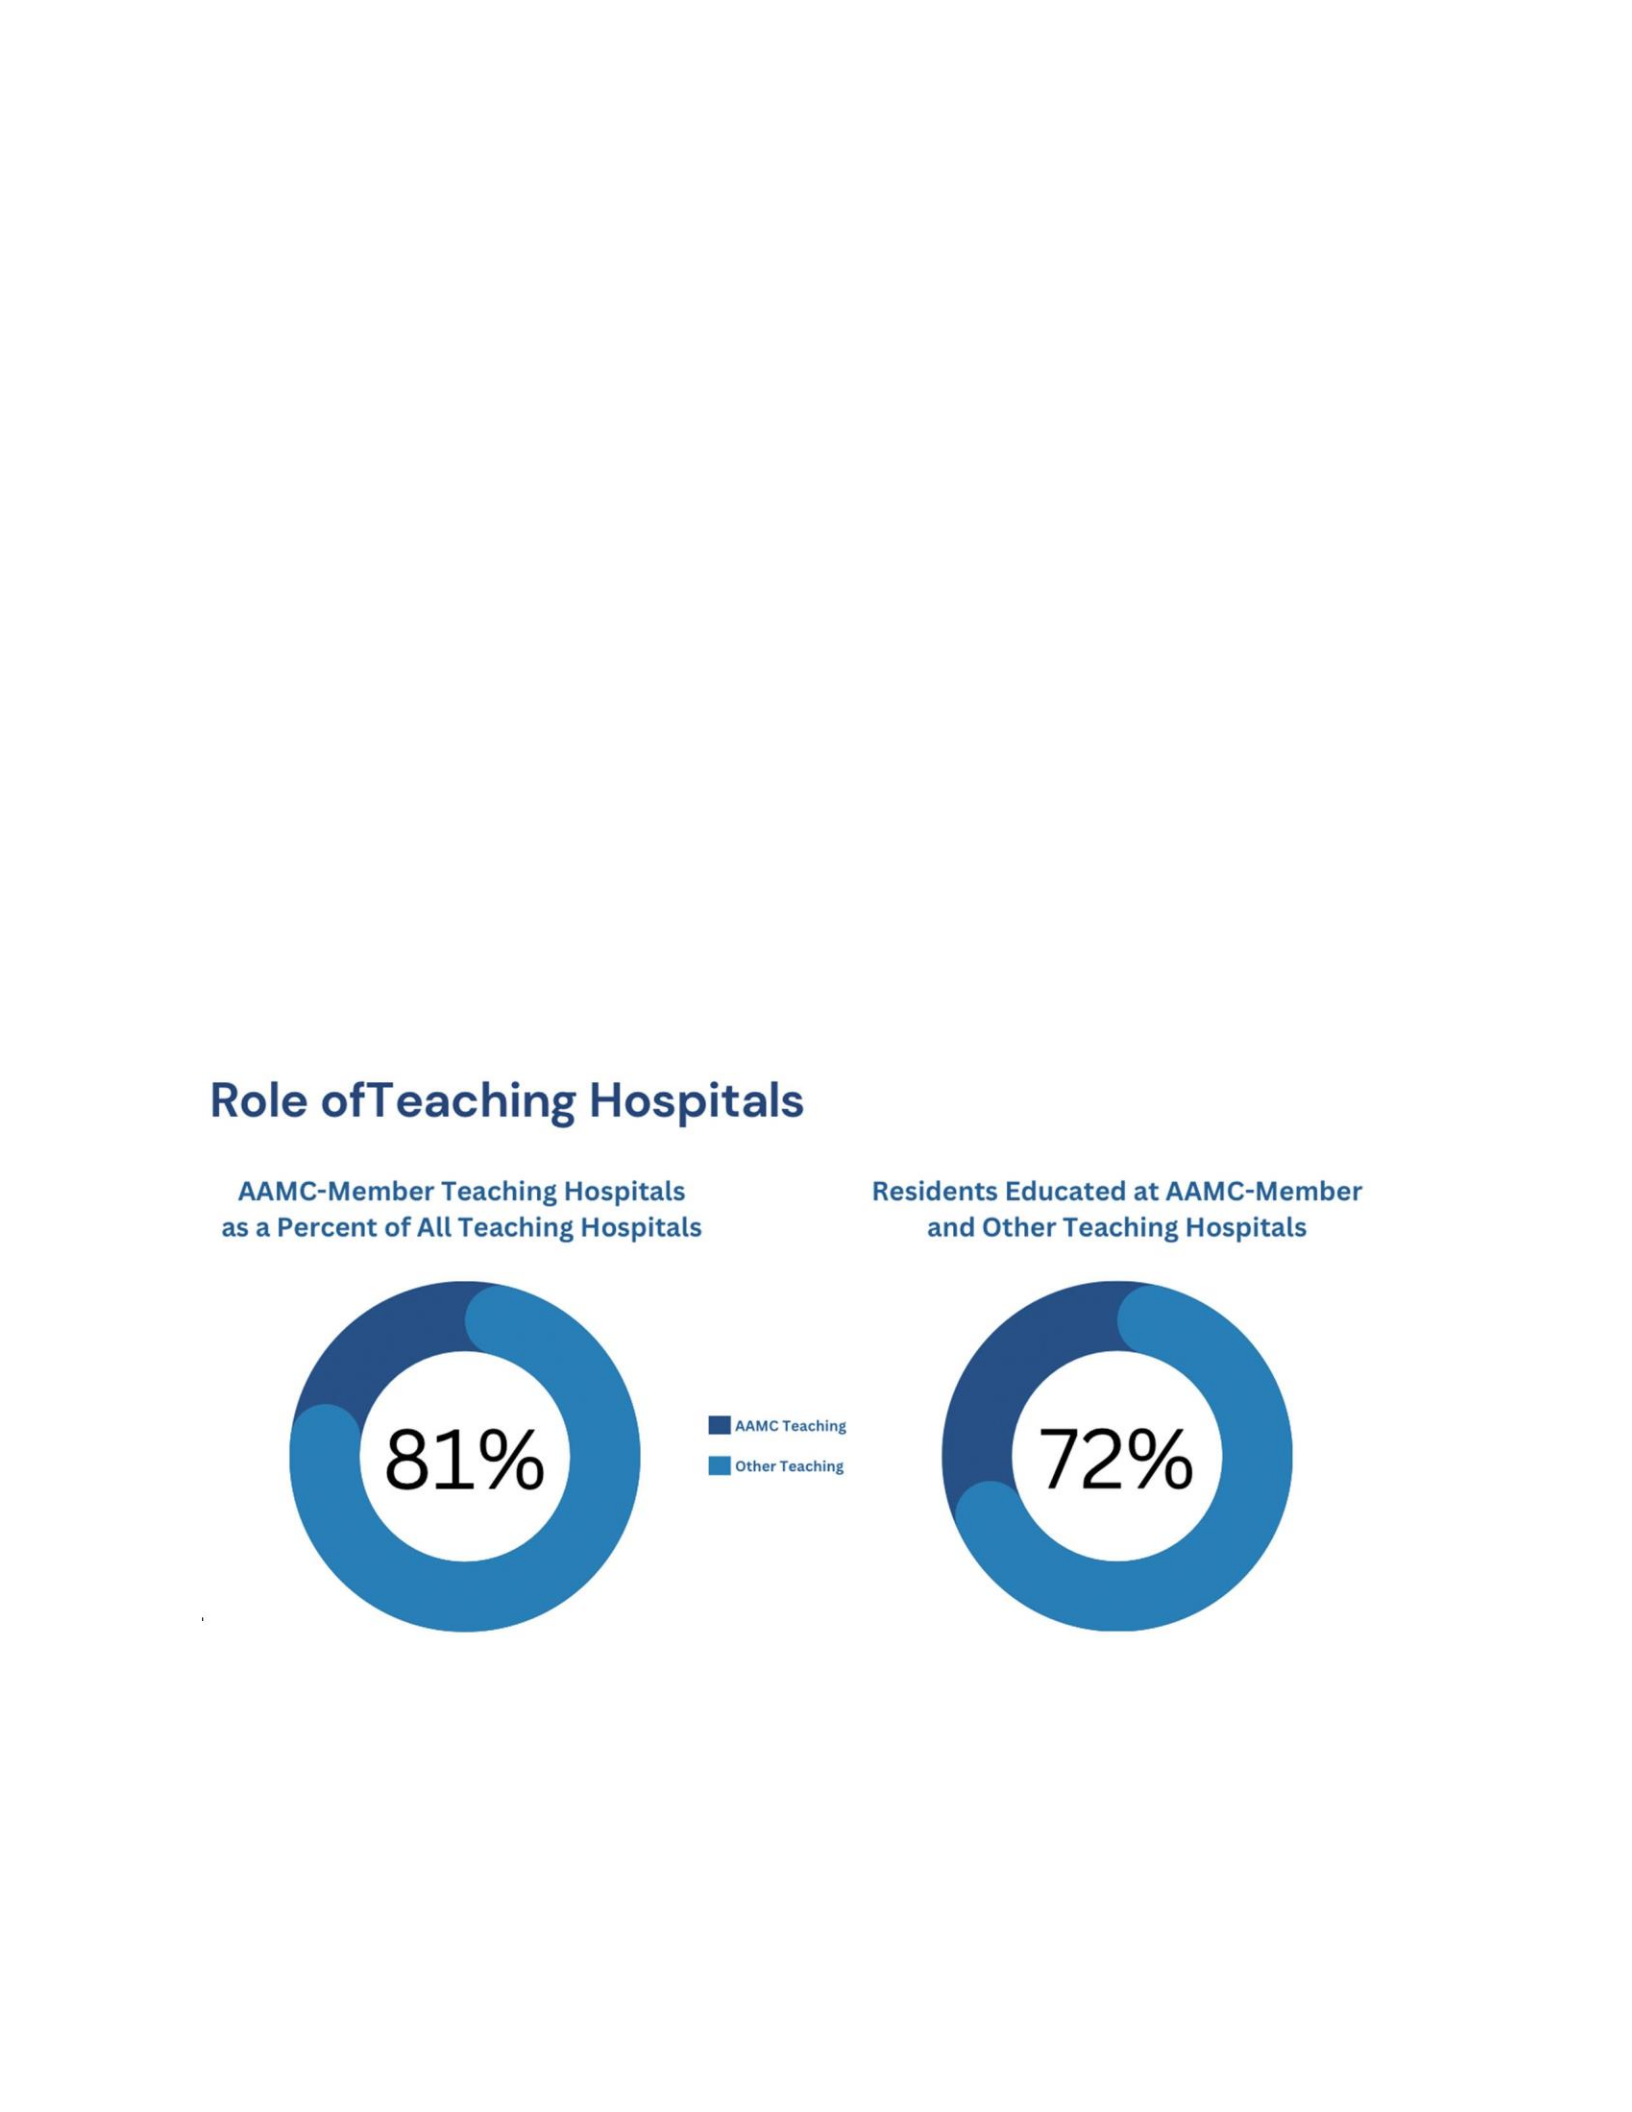
experience to advance students' education and patient care (Liu & Kelz, 2018). As of 2019,
teaching hospitals associated with academic medical centers trained 19% of graduate students
and 28% of residents as seen in Figure 8.
Figure 8
Role of Teaching Hospitals
f
Note. Original figure created based on Economic Impact of AAMC Medical Schools and
Teaching Hospitals, by S. Nienow, E. Brown, M. Hogan, D. Smith, J. Woollacott, and B. Depro,
2022. Association of American Medical Colleges. (https://www.aamc.org/data-
reports/teachinghospitals/interactive-data/economic-impact-aamc-medical-schools-and-
teaching-hospitals). In the public domain.

Hospital System Categorization
Hospital systems have been categorized as community hospitals, federal government or
nonfederal care. According to the American Hospital Association, the majority of U.S. hospitals
are classified as community based (n = 5,139, 84%), compared to nonfederal psychiatric
institutions (n = 635, 10%), federal government hospitals (n = 207, 3%). Two-thirds of
community hospitals are located in large cities (AHA, 2022). Some community hospitals focus
on certain conditions or diseases. For example, specialty orthopedic care or cancer treatment
centers. While others provide general care or have concentrated expertise in a specific medical
area. Community hospitals range in size from six beds to greater than 500 beds (AHA, 2022)
and can also be classified as major, minor or nonteaching facilities. Nonteaching
communitybased hospitals focus on providing essential care for patients by medically trained
clinicians and professional staff, but do not provide medical training and research.
Patients with mental health afflictions that require acute hospital care to treat austere
cases of depression or substance abuse exist in the private sector. There are more than 400
psychiatric care nonfederal hospitals in the United States. Patients that no longer require acute
care but have extreme illness are often cared for at a long-term care hospital. These nonfederal
facilities provide rehabilitative care and medical assistance over protracted periods. Other
private hospitals also are considered to be part of the nonfederal category. The federal
government operates 200 hospitals to provide care for routine medical or surgical conditions for
military personnel. These institutions are governed by the Department of Defense, the
Department of Health and Human Services, or Veterans Health Administration.
In addition to the three classifications described above, teaching hospitals are delineated
as major and minor. As previously discussed, major teaching hospitals are academic medical
centers with an affiliation with a medical school with extensive research projects or clinical trials
to identify care solutions for patients with complex or rare medical conditions. In contrast, minor
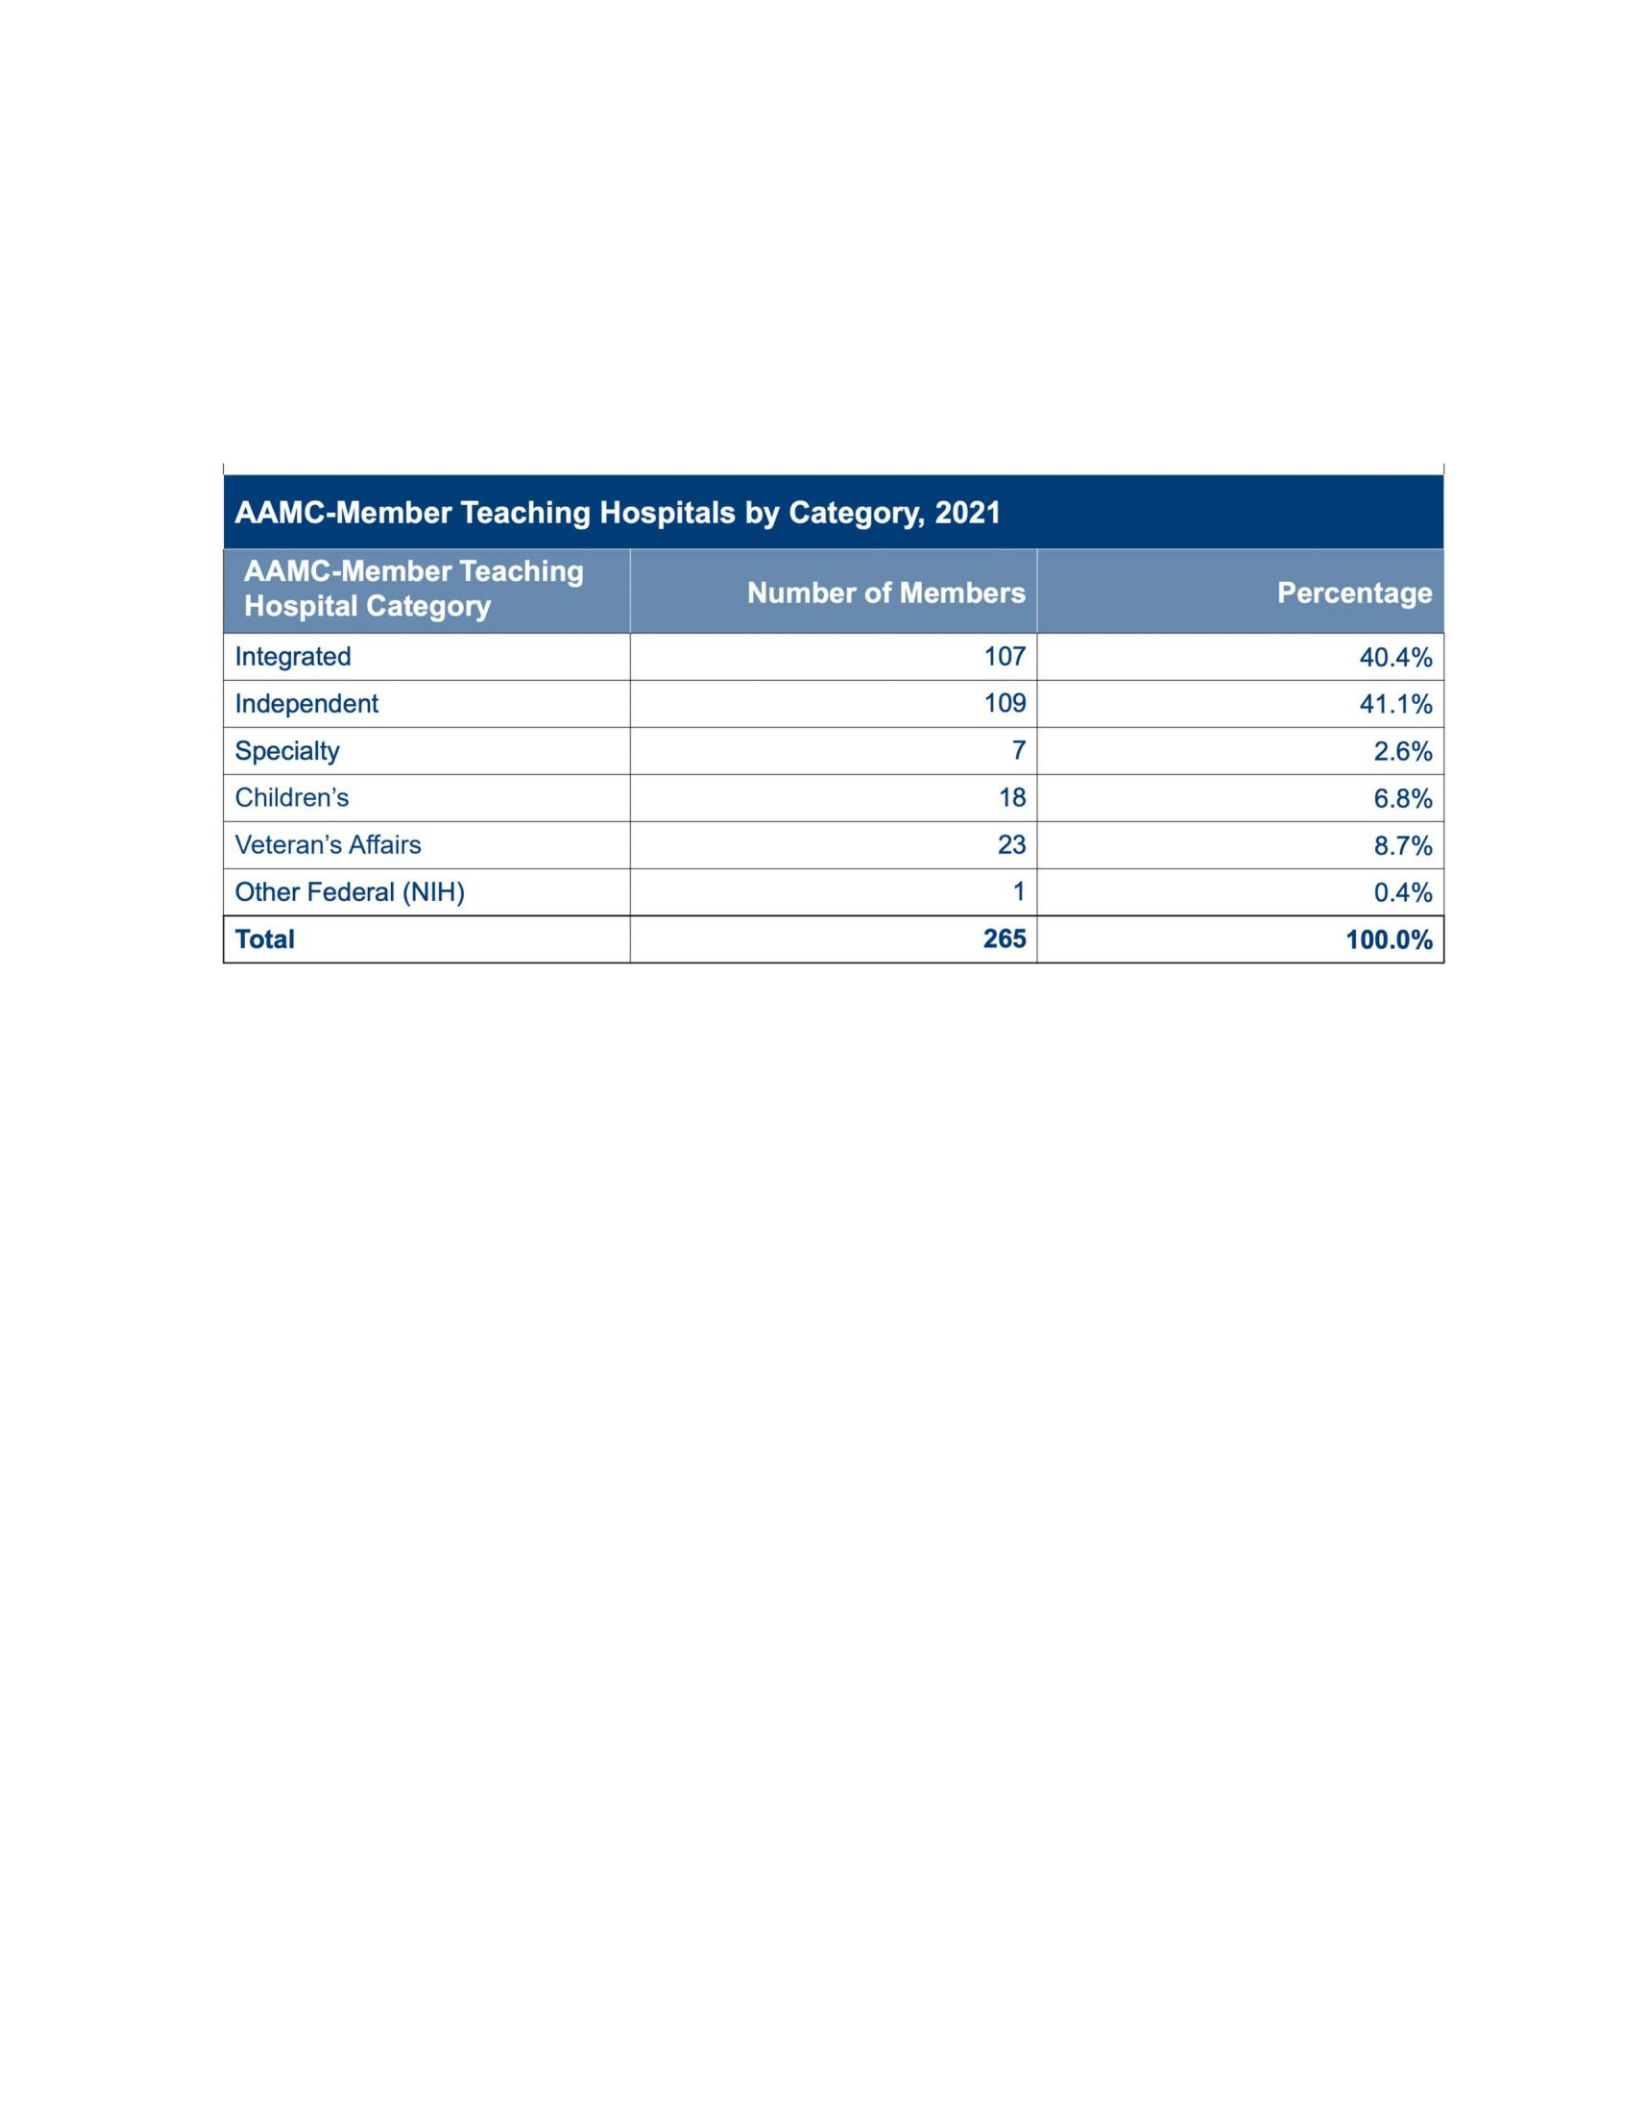
teaching hospitals do not have medical schools. Table 1 presents the AAMC categorization of
teaching hospitals.
Table 1
Categorization of Teaching Hospitals
Note. Original table created based on Economic Impact of AAMC Medical Schools and
Teaching Hospitals, by S. Nienow, E. Brown, M. Hogan, D. Smith, J. Woollacott, and B. Depro,
2022, Association of American Medical Colleges (https://www.aamc.org/data-
reports/teachinghospitals/interactive-data/economic-impact-aamc-medical-schools-and-
teaching-hospitals).
Industry Trends
Academic medical centers are anticipated to hold a lasting, central, and unique position
in the healthcare ecosystem. Throughout history, major medical breakthroughs are attributed to
researchers at academic medical centers who initiated groundbreaking cures like Ebola and
polio vaccines. Without academic medical centers, the medical research community would
experience a tremendous void and lack the infrastructure that provides exposure and enables
clinicians to experience a variety of conditions for healing. Research shows that patients
receiving care at major teaching hospitals have survival odds of 20% higher than in nonteaching
hospitals (L. Burke et al., 2017).
As the pandemic thrust complexities in delivering care, academic medical centers
demonstrated value as a critical institution responding to a public health crisis (Rudoy et al.,

2021). Hospitals augment and extend efficacy within the rest of the health system (World Health
Organization, 2023). More than half of the National Institutes of Health funding awarded to
American scientists are allocated to researchers at academic medical centers (Kirch, 2016). The
discoveries have been estimated to have saved 2.4 million people’s lives since 1991. Further,
academic medical centers partner with communities and community-based programs to tackle
concerns about the lack of access to healthful food, safe housing, and transportation, all of which
contribute to health equity related to the social determinants of health (Flaubert et al., 2021).
Academic medicine plays a pivotal role in U.S. healthcare and globally.
The entire health care industry is experiencing disruption, signs of which were present
even prior to the pandemic (Retchin & Clark, 2005; Stark, 1999). As the pandemic accelerates
transformation, chief executives demonstrated the viability of academic medical center's
tripartite mission (Kenton, 2022). However, the pace of change and impact on the workforce has
worsened due to the pandemic (Gebreyes et al., 2021). Throughout the pandemic, research
discoveries and innovative care for acute patient conditions intersected with training as an
essential role in the nation's health and economy (AAMC, 2021; AHA, 2021).
The pandemic is accelerating transformation of large primary teaching hospitals’ tripartite
mission of research, education and clinical care. As the U.S. population ages and workforce
shortages in physicians and registered nurses widen, chief executives are faced with current
health system operations and building the foundation to weather unknown future disruptions in
teaching and research that improves the health of the nation (AHA, 2022). Historically, the
uniqueness of academic medical centers provided insulation during industry disruptions to
sustain economic stability for the institution (Rudoy et al., 2021). Nonetheless, the
unprecedented convergence of challenging business conditions is applying pressure to maintain
buoyancy in current operations and future projected growth (Nauck et al., 2021).

Academic medical centers are large complex operations that are ill-equipped to pivot to
deploy change strategies agilely (AAMC, 2021; Barta et al., 2019; Swanson, 2022). Despite
academic medical centers centrality to the healthcare system, they face significant challenges in
maintaining status quo operations, especially as emerging disruptors encroach on the sector
(Gebreyes et al., 2021; Swanson, 2022). Disruptions amplify the need for leaders who bring
profound change leadership practices to effectuate the future of academic medical centers and
the industry. Transformational opportunities unveiled as a result of seismic change in hospital
operations, like the COVID-19 crisis, burgeoning labor challenges and uncertainties driven by
multidimensionality, facilitate opportunities for leaders to learn and change (Rudoy et al., 2021).
In a study of academic medical center CEOs, Rudoy et al. (2021) synthesized the 30 hours of
discussion into three categories: being at the cusp of industry and institutional transformation,
capitalizing on the opportunities created by the pandemic, and recognizing the need to
modernize operations.
Labor shortages top the list of short-term future concerns facing academic medical
centers and chief healthcare executives (Swanson, 2022). People are core to everything that
hospital systems do and are the lever or anchor to the tripartite mission of the emerging
workforce (Kenton, 2022). Hospital systems are facing acute labor shortages projected as a
current and future threat to their services and the offerings they can provide patients (Advisory
Board, 2022; Swanson, 2022). Future estimates of the U.S. healthcare workforce project
shortages by 2025. In an independent study commissioned by the AAMC, a shortage of
between 61,700 and 97,000 physicians is projected by 2025, primarily driven by the growth in
the aging population and retirements impending of older physicians (AAMC, 2021; Kirch, 2016).
Hospitals cannot function without skilled nurses (Flaubert et al., 2021). Nursing
shortages have been highlighted by the pandemic. As such, the importance of registered nurses
has increased in awareness. Registered nurses are important to hospital operations as

preceptors for newly minted resident nurses at teaching hospitals. Registered nurses are among
the highest jobs in demand in the U.S. with projected shortages in excess of 1.2 million by 2030
(Auerbach et al., 2016; Bean, 2020; Bureau of Labor Statistics, 2020; Irvine, 2021).
Over time, there has been an evident trend in the complexity of leading an academic
medical center, wherein such leadership extends beyond mere strategies to a focus on
achieving the tripartite mission of operating within highly matrixed organizational constructs
(Khaliq et al., 2006). An organizational structure is a system that frames the way certain
activities are directed to achieve its goals, remain efficient and stay focused (Bolman & Deal,
2008; Kenton, 2022; Schein, 1985). Contemporary organizational structures are synonymous
with matrix management. Drucker (1993), a management theorist, referred to matrix
organizations as system structures that require clear goals, maximized self-discipline throughout
the structure and senior leaders that take personal responsibility for building relationships and
communications.
The nature of tripartite missions is designed around matrix organizational structures as a
means to achieve goals and render outcomes. Within academic medical centers, CEOs will
have matrixed relationships with academic deans, board of directors, and hospital operators to
create concentric support to homogenize each mission independently and collectively (Guzick &
Wilson, 2018). A solo academic medical center executive has matrixed oversight by a president
of the university and the board of directors. Guzick and Wilson (2018) purported that the right
executive in position can be transformational just as the wrong person can be disastrous. For
example, a dean of a medical school and CEO of a hospital can be successful partners as chief
leaders that share common values, goals and leadership styles. Conversely, executives who are
matrixed that are at odds are subject to tension between the two leaders, the functions and can
lead to both entities underperforming.

Academic medical center executives are facing the need to undergo significant
largescale changes if they are to remain competitive or survive in the current market. Change is
particularly complicated in balancing clinical care imperatives with the academic mission
(Evangelides et al., 2015). A new model of leading academic medicine expands the tripartite
mission to embed opportunities for creative inquiry and pioneering. In a world in which
pandemics, injustices, concerns of well-being, epidemics and health disparities require new and
differentiated responses, chief executives in academic medicine are positioned to lead
organizational change (Roberts, 2021).
Industry Threats
Hospitals provide services that most people will need at some point in life (World Health
Organization, 2023). The oath made by academic medical centers to keep people healthy, to
provide research innovations that advance health and lifesaving care are unwavering even in
the face of daunting challenges such as the public health crises (AHA, 2022). Health systems
affect people’s lives and livelihoods which focuses paramount importance on the way they are
designed, lead, and financed. The difference between a well-performing health system and one
that is failing can be measured in death, disability, impoverishment, humiliation, and despair
(World Health Organization, 2023).
However, many health systems have increasingly difficult headwinds to manage the
aftershocks of the most significant crisis in a century (Bardin, 2022). Threats to financial viability
are occurring against the backdrop of inflation, broken links in the supply chain, and historic
workforce shortages that have increased the cost of providing care and educating the next
generation of medical practitioners (American Hospital Association [AHA], 2022; Swanson,
2022,). Stating the obvious, to achieve the tripartite mission of patient care, research, and
educating the next generation of clinicians, academic medical centers must remain financially
viable (Swanson, 2022).

Financial Crises. Hospitals are cornerstones of the community and the U.S. economy.
However, the razor-thin margins characteristic of hospital systems mean that these systems
have become even more strained as the pandemic increased operating expenses (Gebreyes et
al., 2021). For example, dramatic increases in expenses are evident when comparing operating
costs for drugs, labor, and supplies when examining the period from 2019 to 2021. Hospital
expenses and rising inflation are manifesting into financial challenges coupled with the
enormous strain that is placed on the health care workforce (AHA, 2022; Swanson, 2022).
Moreover, acute financial losses during the pandemic are compounded and continue with
inflationary rising expenses, supply chain issues and staffing shortages (AHA, 2022). The
increased expenses and reduced operating margins evident within recent years are not
sustainable.
Prior to the turbulent disruptions academic medical centers currently face, the centers
had a historic trajectory of redefining their position in healthcare delivery as the marketplace
radically transformed (Retchin & Clark, 2005; Stark, 1999). Furthermore, the pandemic has
significantly taxed health care workers in the two years since the outset of the outbreak (AHA,
2022; Ng et al., 2021). Notably, three categories have driven hospital expenses between 2019
and 2021, drug costs, labor and supplies, as illustrated in Figure 9.
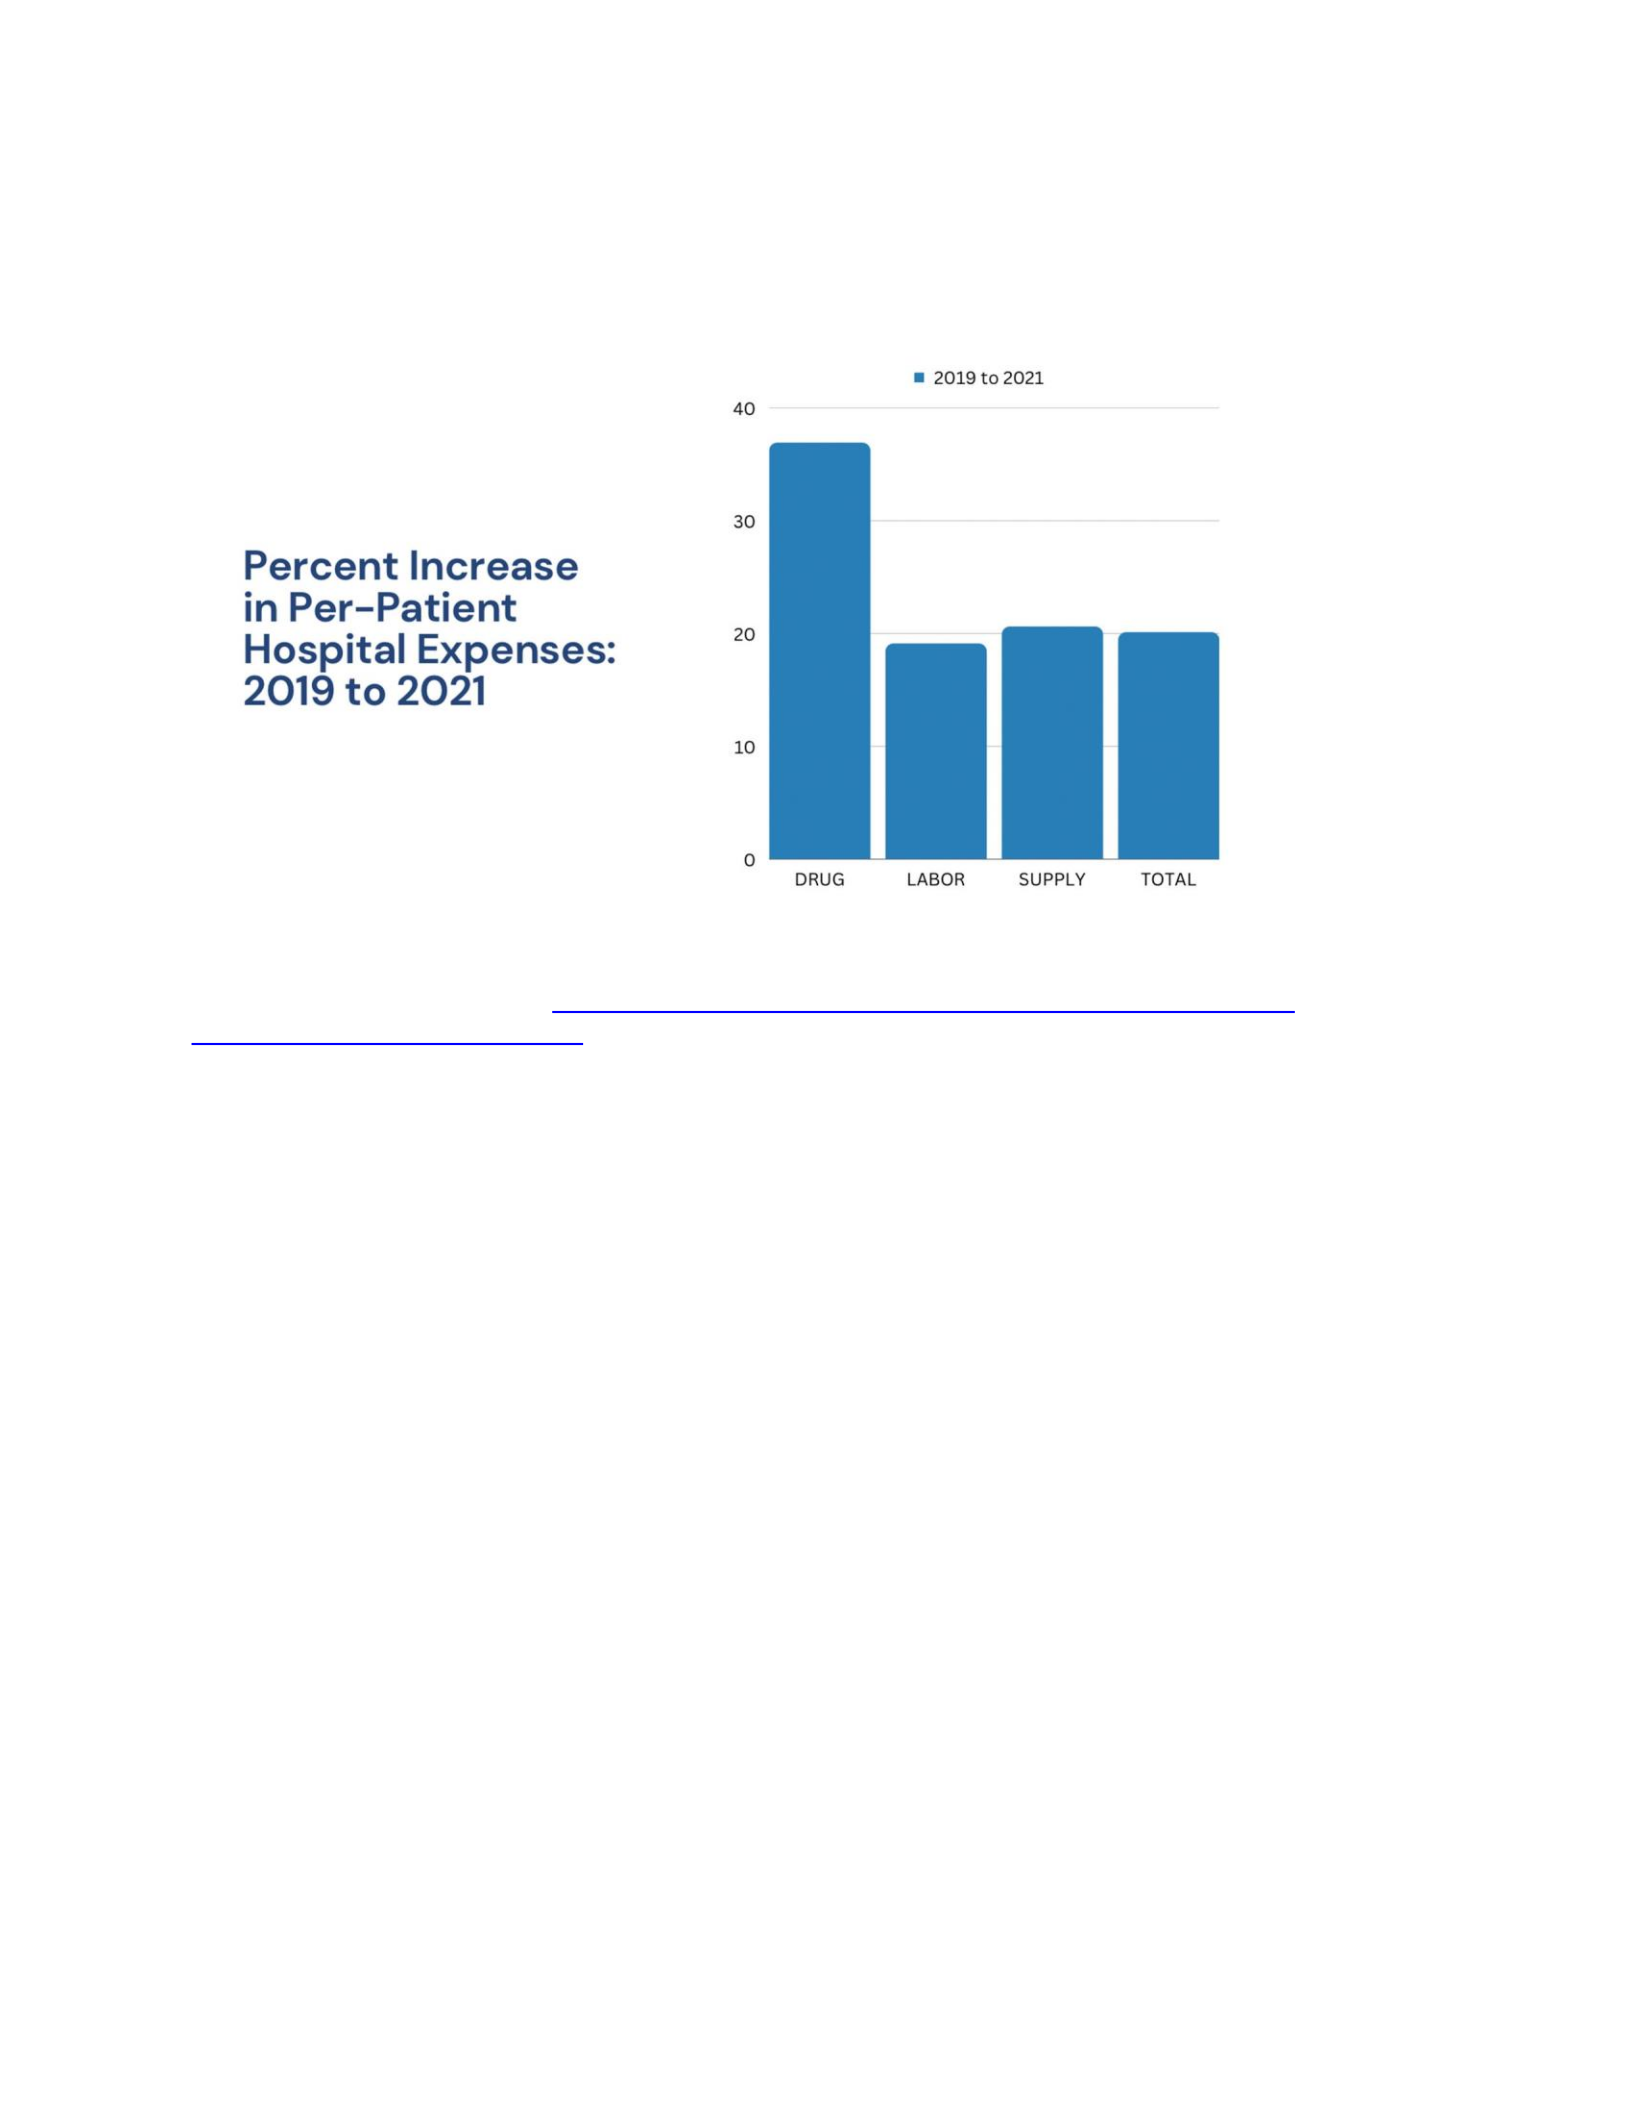
Figure 9
Percent Increase in Per-Patient Hospital Expenses: 2019 to 2021
Note. Original figure created based on National Hospital Flash Report: January 2022, by E. Swanson,
January 2022, Kaufman Hall. (https://www.kaufmanhall.com/insights/research-report/national-
hospitalflash-report-january-2022). In the public domain.
Labor Shortages and Disengagement. By far, the most pervasive challenge facing
health system leaders are workforce shortages and employee discontent (AHA, 2021; Figueroa
et al., 2019; Greiner & Knebel, 2003; Nienow et al., 2022). Health consumers are experiencing
limited accessibility woes in obtaining accessibility to physicians with the credentials and
medical outcomes desired (Figueroa et al., 2019). Instead, consumers seeking physician
reviews turn to unsubstantiated online reviews to ascertain uninformed assistance with traits like
wait times, staff relations. While benefits of the platform’s accessibility are evident, a missing
element is the ability to evaluate a physician’s skill level to care for health needs. A recent study
by the AAMC (2021) projects physician shortfalls up to 139,000 physicians by 2033. The AAMC
study points out that the number of physicians reaching retirement age is growing which will
contribute to the shortage. For example, two out of five actively employed physicians will reach
65 or older over the next decade. Each physician retirement potentially impacts healthcare.

Labor costs account for more than half of hospitals’ total operating costs (AHA, 2021,
2022; Morse, 2022). Hospitals are experiencing nurse shortages now and are forecasted to
continue in the future (Buerhaus, 2021; Bureau of Labor Statistics, 2022). Staffing shortages
have pushed hospitals labor cost up due to expensive contract staff that are hired to augment
less full time staff. Contract labor across U.S. hospitals is close to 500% higher than the
expense before the pandemic (American Hospital Association, 2022; Swanson, 2022). Evidence
of the staffing dilemma is in the increase of job postings for contact or travel nurses. Contact or
travel nurses over a three-year period, between January 2019 to January 2022 affected the
increase in job postings by 120%. Expenses for workforce pay, overtime due to worker
shortages, and contracted temporary registered nurses increase the strain on financial and
human resources (Morse, 2022).
Clinician and health care provider shortages are not emerging concerns. Nursing
shortages that currently exists have been forecasted since the early 2000s. Buerhaus et al.
(2000) forecasted a nurse shortage of 400,000 by 2020 further suggesting the inadequate
supply of labor to meet the clinical demand to provide care for patients. Predictions of more than
500,000 nurse shortages by 2030 were a concern before the pandemic (Zhang et al., 2018). A
contributing factor in the projected nurse supply and demand gap is the aging population of the
nurse workforce. In 2000, the average age of employed RNs was 43.3 (Spratley et al., 2002).
More RNs and physicians are over 50 and 55 respectively (U.S. Department of Health and
Human Services, 2019).
The RN shortage is exacerbated by reduced numbers of new recruits and nurse
preceptors available to train new entrants into the profession. Accelerated retirements or
industry exits are contributory factors to the burgeoning labor supply of RNs. A leadership
imperative is imminent for healthcare systems to adopt to the multidimensional impact to recruit
and retain generationally diverse workers who may not value or tolerate the organizational

culture and tactics of the past and insist on schedule flexibility (Dickson, 2015). Conversely, the
shift suggests healthcare organizations find it necessary to adapt existing practices to compete
with professions outside the industry. These practices would include increasing pay, improving
benefits, focusing on belongingness as a differentiator, or offering greater flexibility in work
schedules (Subramanian & Washington, 2022).
Pandemic aftershocks are a contributing factor to recruitment, staffing and retention of
people in the healthcare profession. A report from the Office of Inspector General U.S.
Department of Health and Human Services (2021) suggests people belief that future conditions
will worsen. In addition, the report showed that hospitals expressed concern that new clinical
graduate providers, such as nurses, may not have gained sufficient experience in care for things
other than COVID-19. More optimistically, evidence of improvement is in the stark increase in
the number of applicants applying to medical schools in 2020 and 2021, as reported by the
AAMC (2021). As a comparison, applicants increased by 17% in 2021 versus typical increases
of 2-3% in 2019. Similarly, the percentage of student acceptances increased by 1.8% and 2.6%
in 2020 and 2021, respectively (AAMC, 2021). Also, among the 22,000-plus students who
began medical school this fall, those self-identified as Black or African American rose by 21.0%
from 2020-21, followed by increases of 8.3% among Asian students and 7.1% among those of
Hispanic, Latino, or Spanish origin (Boyle, 2021).
Shortages of skilled clinicians together with an overworked staff, personnel placed in
unfamiliar roles or teams, or lack of staff heightens many types of risks (Derse & Bateman,
2021). When staffing levels of clinicians drop, hospitals experience an increase in workplace
injuries that result in downtime from workers’ compensation claims. Another factor of lower
staffing levels is the increase in medical errors, some resulting in liability assertions. As staffing
shortages prevail there is an association with increased workplace violence and wage and hour
legalities.

Changes made to adapt to staff shortages create other risk for executives to mitigate
(Insider Intelligence, 2023). Digital adaptations in healthcare pose solutions as well as risks
robotics, artificial intelligence, tele-medicine, cyberattacks, data breaches, wearables or
smartphones are among the emerging digital elements that either advance or amplify risk to
health systems (Donald, 2019a). These advancements risk can impact patients and health
systems. Using artificial intelligence to inform leadership decision-making has complexities that
risk poor outcomes or myopic decisions. Novel digital advancements will require leaders to
identify and implement risk mitigation strategies and tactics (Derse & Bateman, 2021; Donald,
2019a; Insider Intelligence, 2023).
Leadership Cultures and Trends
In the literature, leadership is conceptualized as a process of influence that elicits the
context to achieve goals through a shared vision (Senge, 1995). Leadership styles and culture
are widely characterized in the literature with a plethora of research or empirical studies of
leading businesses. However, most theories of leadership originated from a business context
and were later applied to healthcare (Al-Sawai, 2013). Within healthcare, there is a dearth of
recent literature on what characterizes leadership styles and organizational culture in large
hospital systems. Leadership research specifically related to the healthcare industry is limited
with minimal information available about chief executives’ values, experiences, or leadership
styles (Janssen, 2004).
Common Leadership Styles and Cultures in Large Hospital Systems
Modern medical systems are one of the most complex organizations on the globe
(Cosgrove, 2016). Healthcare chief executive challenges are unique to the industry in that they
must direct their workforce’s efforts to benefit patients, communities, and the organization
(Hargett et al., 2017). Al-Sawai (2013) suggests the need for adaptation of leadership
approaches to optimize effectiveness in large healthcare systems. While there is limited

research that exists on the characteristics of chief executives leading large hospital systems,
there is congruence that a prime characteristic of hospital CEOs is the important role they play
in setting the vision, determining the strategic goals, and providing executive oversight of
executing change that promotes positive experiences for patients and employees (Al-Sawai,
2013; Cosgrove, 2016; Galstian et al., 2018; Goodall, 2011).
Galstian et al. (2018) researched whether gender, education, or tenure within the
organization were characteristics of hospital CEOs. If so, the researchers examined aspects
associated with positive patient experience scores. The findings indicated that hospitals that
employ longer-tenured CEOs or female CEOs were attributed to positive patient experience
scores.
Studies in a healthcare setting have also shown that inclusive leadership practices have
lessened the effect of role-based status on psychological safety (Nembhard & Edmondson,
2006). Inclusive leadership is characterized as an essential factor in ensuring diverse thinking
and voices are solicited, respected, listened to, and incorporated in getting people on board with
new ideas and different ways of doing things (Roberson & Perry, 2022). In a thematic analysis of
leaders’ responses to questions regarding their perceptions and demonstration of inclusive
leadership, conceptualization themes emerged relating to valuing, understanding, the utilization
of differences to encourage collaboration and shared identity.
Further, research findings highlight the importance of inclusivity in leadership to garner
creativity and generate trust between team members (Roberson & Perry, 2022). Creativity is
critically important in every sector of an economy considering the seminal role that employees
play in the success of an organization’s performance, including healthcare systems (Ahmad et
al., 2022; Fu et al., 2022; Imran et al., 2018; Scarmozzino & Corvello, 2016). Employees’
creativity primarily hinges on inclusive leadership and different styles drive workplace behaviors

(Bannay et al., 2020; Deng et al., 2022). Yet, the role of inclusive leadership in the healthcare
sector is an understudied area (Fu et al., 2022).
Edmondson (2018) describes psychological safety at work as an environment where
people are allowed to ask questions and innovate without fear of retribution, embarrassment,
retaliation, or negative career-limiting consequences. It is researchers’ shared belief that
psychological safe spaces induce feelings that people can take interpersonal risks to express
themselves without negative consequences of embarrassment, ridicule, or shame (Carmeli &
Gittell, 2009; Kessel et al., 2012; Rathert et al., 2009; Wanless, 2016; Wetzel et al., 2012).
Juxtaposed with anxiety filled environments, psychologically safe workplaces enable people to
engage, learn, connect with others and change to focus on activating and accomplishing goals,
regardless of the inevitability of discomfort that comes with new experiences or expressing new
ideas (Edmondson & Lei, 2014; English & Stengel, 2010; Wanless, 2016). Pronounced
hierarchical constructs are less conducive to fostering environments that cultivate spaces for
people who are lower in the hierarchy to feel safe to engage in the group (Kahn, 1990; Netzley
& Rath, 2012; Wanless, 2016). Hence the importance of having the leader of an organization or
group convey and demonstrate the importance of everyone’s contribution to facilitating greater
engagement and psychological safety (Huo et al., 2010; Nembhard & Edmonson, 2006).
Psychological safe spaces are essential in teaching hospitals because they afford
students, residents and every person to learn and innovate (Hardie et al., 2022). Knowing that
CEOs set the stage for organizations, highlights the need for them to visibly demonstrate
inclusive leadership (O’Donovan & McAuliffe, 2020). Inclusive leadership efforts foster
psychological safety within hospital settings, providing the opportunity for role modeling
behaviors to cultivate the phenomenon across teams and the healthcare system (Kessel et al.,
2012; O’Leary, 2016; Weiss et al., 2018).

Culture is the collective set of shared attitudes, goals, behaviors and values that shape
hospitals outcomes and future growth. Culture is determined by three primary factors: leaders,
values and the environment (Deal & Kennedy, 1982; Kouzes & Posner, 1995; Schein, 2010).
Schein (2010) describes culture as a pattern of basic assumptions that a group learns and that
is taught to new members so that they know the proper way to perceive, think, and feel.
Organizational culture is characterized by researchers as the shared assumptions that
guide the member’s behaviors in ways that affect how people and groups interact with each
other, key constituent stakeholders, clients, and customers (Ravasi & Schultz, 2006). In the
healthcare setting, culture begins with leadership. As Denison (1990) posits, culture is a key
predictor of organizational effectiveness through leadership.
Common Backgrounds and Qualifications of C-Suite Healthcare Leaders
Hospital CEOs come from varied backgrounds that are different in levels of advanced
education, breadth of knowledge that demonstrates a commitment to the profession, and
relevant healthcare management certifications. One popular example of certification distinctions
for hospital CEOs is Fellow of the American College of Healthcare Executives. The Bureau of
Labor Statistics (2022) amplifies communication, decision-making, leadership capabilities, time
management and problem-solving among the key skills that are most important for top
executives. Goodall’s (2011) research elucidated that hospitals run by physician CEOs scored
25% higher in quality of care outcomes and patient satisfaction. At the time of the study, of the
6,500 U.S. hospitals, 235 were led by physicians. The research advocates that physician
practitioners make the best leaders. However, evidence suggests there is a formidable gap
between physician leaders possessing the expertise to leadership success (Blumenthal et al.,
2012; Bohmer, 2012).
Healthcare Leaders’ Role in Addressing Industry Challenges
Health care systems face major challenges that require CEOs to be prepared for reform
(Greiner & Knebel, 2003). Crisis management over the decades has taken different shapes and

complexities. For example, attention on quality in health care as a crisis requiring leaders is well
recognized as a concern (Aiken et al., 2002; Chassin, 1998; Chassin & Galvin, 1998). During a
summit of health care leaders, a rally call to health professionals to establish themselves as
leaders to bring about change to improve health care systems quality, workforce and education
was solicited (Shine, 2002). Health leaders are at the core of the redesign of health care
systems (ACHE, 2022a; Figueroa et al., 2019).
Hospital leaders play a critical role in recovering from crises while addressing immediate
patient care imperatives. Accordingly, healthcare executives are looking toward the future to
position their organizations for success. Succession planning and a focus on developing a
pipeline of leaders equipped to address the challenges of tomorrow are inclusive of executives’
focus (Collins & Collins, 2007). Research indicates that an entire industry can experience the
impact of decisions when one major organization’s leadership establishes policy or practice
changes (Derenoncourt et al., 2021; National Bureau of Economic Research, 2021). Hospital
systems are facing indelible paradigm shifts in doing things differently from the way they have
done for years. Shifts in the economy and the workforce continue to add complexities to
leadership challenges in leading academic hospital systems (Lantz, 2008; Weintraub & McKee,
2019; Wheatley, 2010). As turnover among healthcare executives continues to reach new levels,
the dilemma of continued disruption will exacerbate within the industry and hinder hospitals’
organizational performance (Wheatley, 2010).
Berwick (2003) underscored the importance of the need to bring about change in
healthcare systems’ quality, clinical education and acknowledged the difficulties in bringing
about change in clinical education to improve the health status and functions of the U.S.
population. Berwick (2003) argues this imperative is the true north for the industry. Two decades
later, the industry is at the precipice of change.

Chief Executive Transition
There is a paucity of organizational research on managing chief executive transitions in
healthcare. Definitions of leadership transitions are explained in various ways (Allison, 2002;
Wiggins, 2019). Common explanations for what constitute an executive transition are studied
generically through the lens of leader transitions, which are grouped into several categories.
Turning to several scholars' fundamental definitions of transitions is instrumental in examining
the phenomenon.
Multiple scholars speak of transitions as a continuous process of change (Anderson et
al., 2021; Sivapregasam et al., 2019; Wiggins, 2019). Levinson (1986) describes transitions as a
period between two periods of stability. Bridges’ (2009) work distinctly differentiates between
change, an external occurrence, versus transition, an emotional process leaders experience as
a result of a change. A study on internal promotion into leadership has defined leader transitions
as the vertical ascension to a more senior role within an existing organization (Terblanche et al.,
2018).
Reupert (2020) posited that unprecedented forces shape people’s lives bringing
tumultuous transitions to navigate between chaos and complexity. In the organizational context,
researchers suggest significant transitions are defined by leaders assuming new roles in the
occurrence of mergers and acquisitions, divestitures, compensation, or restructures
(Chinyamurindi, 2012; Manderscheid & Ardichvili, 2008). Emerging research presupposes that
leader transitions will be dramatically impacted over the next decades that are characterized by
increasing complexities of shifts in population, change in cultural diversity, and the ways that
people work, are all elements of the backdrop of executive transitions (Fouad, 2019; Gerstorf et
al., 2020).
Transitions are also defined as a period between leadership roles (Watkins, 2003).
Additional definitions of transition in the literature are described by the time from the promotional

move or entry into the organization through the first 18 months in the chief role (Chandran,
2015; Chandran et al., 2015; Wiggins, 2019). Variations in the length of transitions range from
six months to up to three years (Downey, 2002; Gabarro, 2007; Gilmore, 1988; Manderscheid &
Ardichvili, 2008; Watkins, 2003). Successful transitions are denoted by how aligned objectives
are to garner support and deployment of the organization’s resources during the CEO’s tenure
(Chandran, 2015).
In addition to the physical change and timeframe of transitions, the literature also defines
the psychological processes leaders undergo. Bridges (2019) asserts that a continuous
psychological process exists that requires learning new perspectives and adopting behaviors in
concert with the leadership transition. Transition happens simultaneously with the psychological
process and the leaders’ experiences of anxiety, stress, or alienation. The psychological
demands that leaders experience in adapting to more senior levels in the organization are part
of the transition process (Gill, 2017). Conversely, if sufficient psychological conditions exist that
constitute a transition experience, it is argued that a physical change is not required (Ashforth,
2001).
CEOs are positioned at the pinnacle of the organization. Chief executive transitions are
unique because of the critical success factors associated with the position in organizations
(Wiggins, 2019). Managing the departure of one leader and finding the next is latent with risks to
the organization’s stability. Hiring the wrong leader is the most salient risk that causes a threat to
the viability of the organization (Nazemian, 2021). The literature highlights the challenges of
leadership transitions and the associated costs of failure (Charan et al., 2011; Watkins, 2013).
As chief executives in the baby boomer generation age over the next decade, many will step
away from their positions which will open opportunities for the next generation of CEOs (Byrnes
& Taylor, 2015). The likelihood of chief executives adjusting theory perceptions, interpretations
and understanding of the role, themselves in the role over time makes transitions unique in the

experience of reconstructing their beliefs and actions of their current interactions and
experiences that contribute to organizational change (Tsoukas & Chia, 2002).
History of the Study and Practice of Executive Transition
Evidence-based studies on chief executive transitions related to this study is limited in
the literature. Instead, practitioner opinions, models, commentaries, and quantitative reporting
on chief executives’ movement dominates the literature with a broader tilt to leadership
transitions. Khaliq et al. (2006) describe executive appointments as a traumatic event for
hospitals that impacts staff, patients and communities (Weil, 2006).
Healthcare is lagging behind other industries and corporations in succession planning
and retaining senior leadership talent (Blouin et al., 2006; Collins & Collins, 2007). Succession
management as a business strategy in healthcare began gaining momentum from the
escalation of the supply and demand concerns escalated for knowledge workers and nursing
(Carriere et al., 2009; Collins & Collins, 2007). A lack of consistent workforce planning by
hospital systems has resulted in a dearth of successful succession planning frameworks and
strategies for executives as well as mid-level leaders in the healthcare industry (Carriere et al.,
2009).
Succession planning and management is a systematic endeavor to ensure leadership
continuity, protect intellectual capital and preserve institutional knowledge for the future viability
of an organization (Hassan & Nasibollah, 2016). Research shows that 97 hospital CEOs
changes in 2022 with reasons varying between retirement, termination, pursuit of new
opportunities or stepping down to take on other high level roles within the same organization
(Baxter, 2022; Bean, 2020; Challenger, Gray & Christmas, Inc., 2022). Garman and Tyler (2004)
research showed that only 15% of independent hospitals had a succession plan for the sitting
CEO. This highlights the ongoing reticence of some boards and incumbent CEOs to plan for
executive transition. Kovner (1988) argues against external successors based on the premise

that the success of a CEO at one organization is not a predictor of success at another primarily
because the other organization may be facing fundamentally different business challenges.
Rothwell (2015) states that absence of succession, organizations will face problems
such as: critical positions going unfilled, lack of provisions for replacing potential leader exits,
capability gaps among the successors in the organization and diminished retention of talent in
the organization. Failure to have a multi-tiered transition process potentially has adverse
consequences with other key members departing the organization. An examination of CEO
turnover over a 20-year period shows attrition ranging from 14 to 20% in 2002 and remaining at
a steady rate through 2022 (ACHE, 2022b; Challenger, Gray & Christmas, Inc., 2022;
Healthcare Executive, 2003; Khaliq et al., 2006).
Taking into consideration the turnover of CEOs, research indicates chief level transitions
ensue with changes made at the top of the pyramid. Khaliq et al. (2006) research amplified the
point that CEO transitions may trigger other chief executive level leader exits. The categories of
chief executives and support functions included: chief operating officer, chief human resource
officer, chief financial officer, chief nursing officer, chief medical staff officer, chief information
officer, vice president, associate administrator, and assistant administrator. The data from
respondents is shown in Figure 10, indicating that 97% indicated that within one year after the
CEO left the organization vice presidents departure as well. Similarly, the CEO participants of
the survey reported 77% of the chief medical staff officers, 42% of chief financial officers, 52% of
the chief operating officers, 37% of chief human resources officers, 26% of the chief nursing
officers, and 14% of the chief information officers occurred within one year of the CEO turnover.
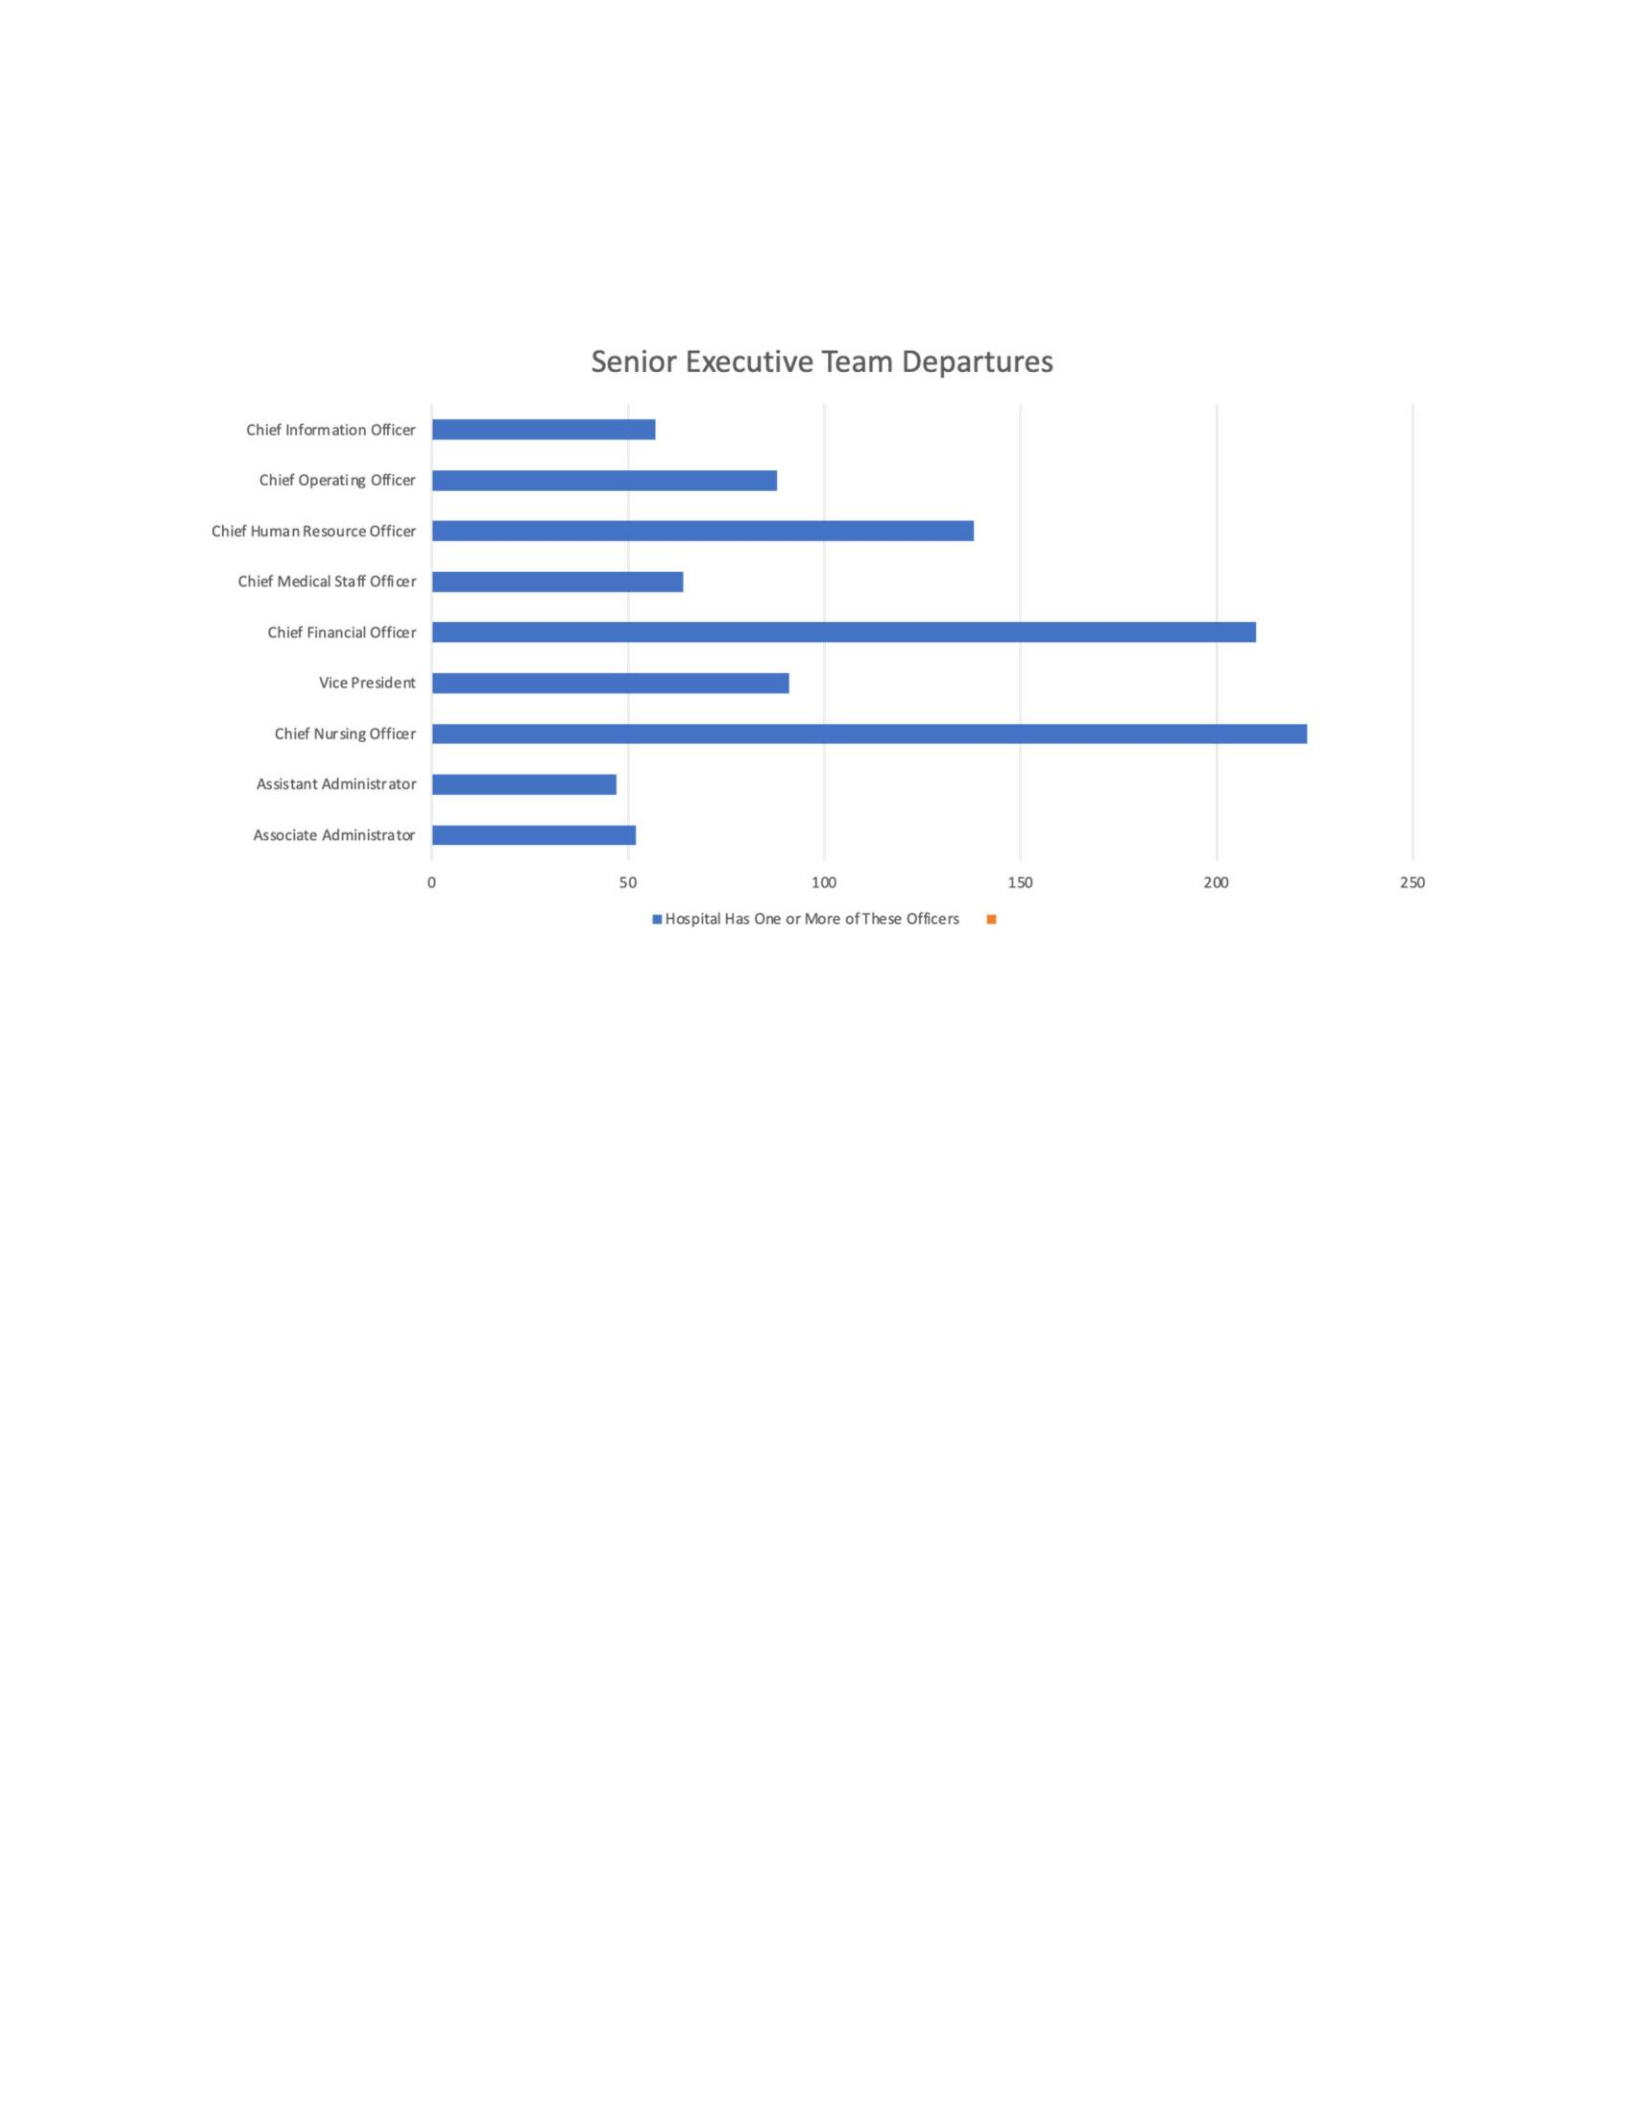
Figure 10
Senior Executive Team Influence of Chief Executive Departure
Note. Original figure created based on The Impact of Hospital CEO Turnover in U.S. Hospitals:
Final Report, by A. A. Khaliq, D. M. Thompson, and S. L. Walston, 2006. Department of Health
Administration and Policy, University of Oklahoma. (https://www.ache.org/-
/media/ache/learning-c enter/research/hospital_ceo_turnover_06.pdf). In the public domain.
While the escalated turnover for healthcare CEOs is stabilizing, hospitals remain the
epicenter of challenges. The multifactorial factors of change place extraordinary strain on
leading through uncertainty. Staffing needs and demand shortages, inflationary operating
pressure, geopolitical unrest, and legislation on adoption are amongst the pressing factors in
consideration for transitioning executives.
The Executive Transition Process
Bridges’ (2009, 2019) distinction between change and transition is applicable to this
study. The phenomena are differentiated as change becomes the circumstance that affects the
person and transition reflects the process of cognition and psychological sensemaking ignited
by the change (Bridges, 2003). In contrast, Ashforth (2001) argues that a physical change in
roles is not a requirement when the changes in the psychological conditions sufficiently
constitute the experience of a transition. Transitions are referred to as an integration and further

explained as the way a leader builds awareness and understanding of the organization’s
purpose, strategic goals, and preferred performance expectations (Bond & Naughton, 2011).
A key factor of the distinction is that changes are experienced as an event that is defined
by its outcome-driven to reach a goal. Transitions begin with letting go of elements that no
longer serve a person’s situation or inadequately provide for the current stage of work or life
they are experiencing. The premise outlined suggests unless transition happens, change will not
work, because it does not stick. A transition is explained as an event that disrupts the roles,
relationships and routines of the people experiencing the transition (Chickering & Schlossberg,
2002).
Every transition begins with an ending as a process that occurs over time (Schlossberg,
2011). Bridges (2019) purports that transitions mark the turning points on a pathway of growth
as a natural progression of disorientation and reorientation. The model of change outlines
transition over three stages that incite individual and psychological changes: ending, neutral
zone, and new beginnings (see Figure 11). Letting go resemble grieving of what people have to
let go of before incorporating new ways of being, ending, neutral and new beginnings. As
Bridges (2003) describes, ending is letting go of what will no longer exist and managing the loss.
During the neutral time, psychological realignment happens to shift from old to new realities.
The third stage is new beginnings where new identities and values emerge and the momentum
of energy returns. While we are cognitively aware that a change is occurring, we are less
attuned to our emotional response to the phenomenon (Bridges, 2003, 2019). Paying careful
attention to emotional responses of transitions through each stage increases the likelihood that
positive changes will have a lasting effect and that difficult changes will give way to the
possibility of healing and growth (Bridges, 2003; Shy & Mills, 2010).
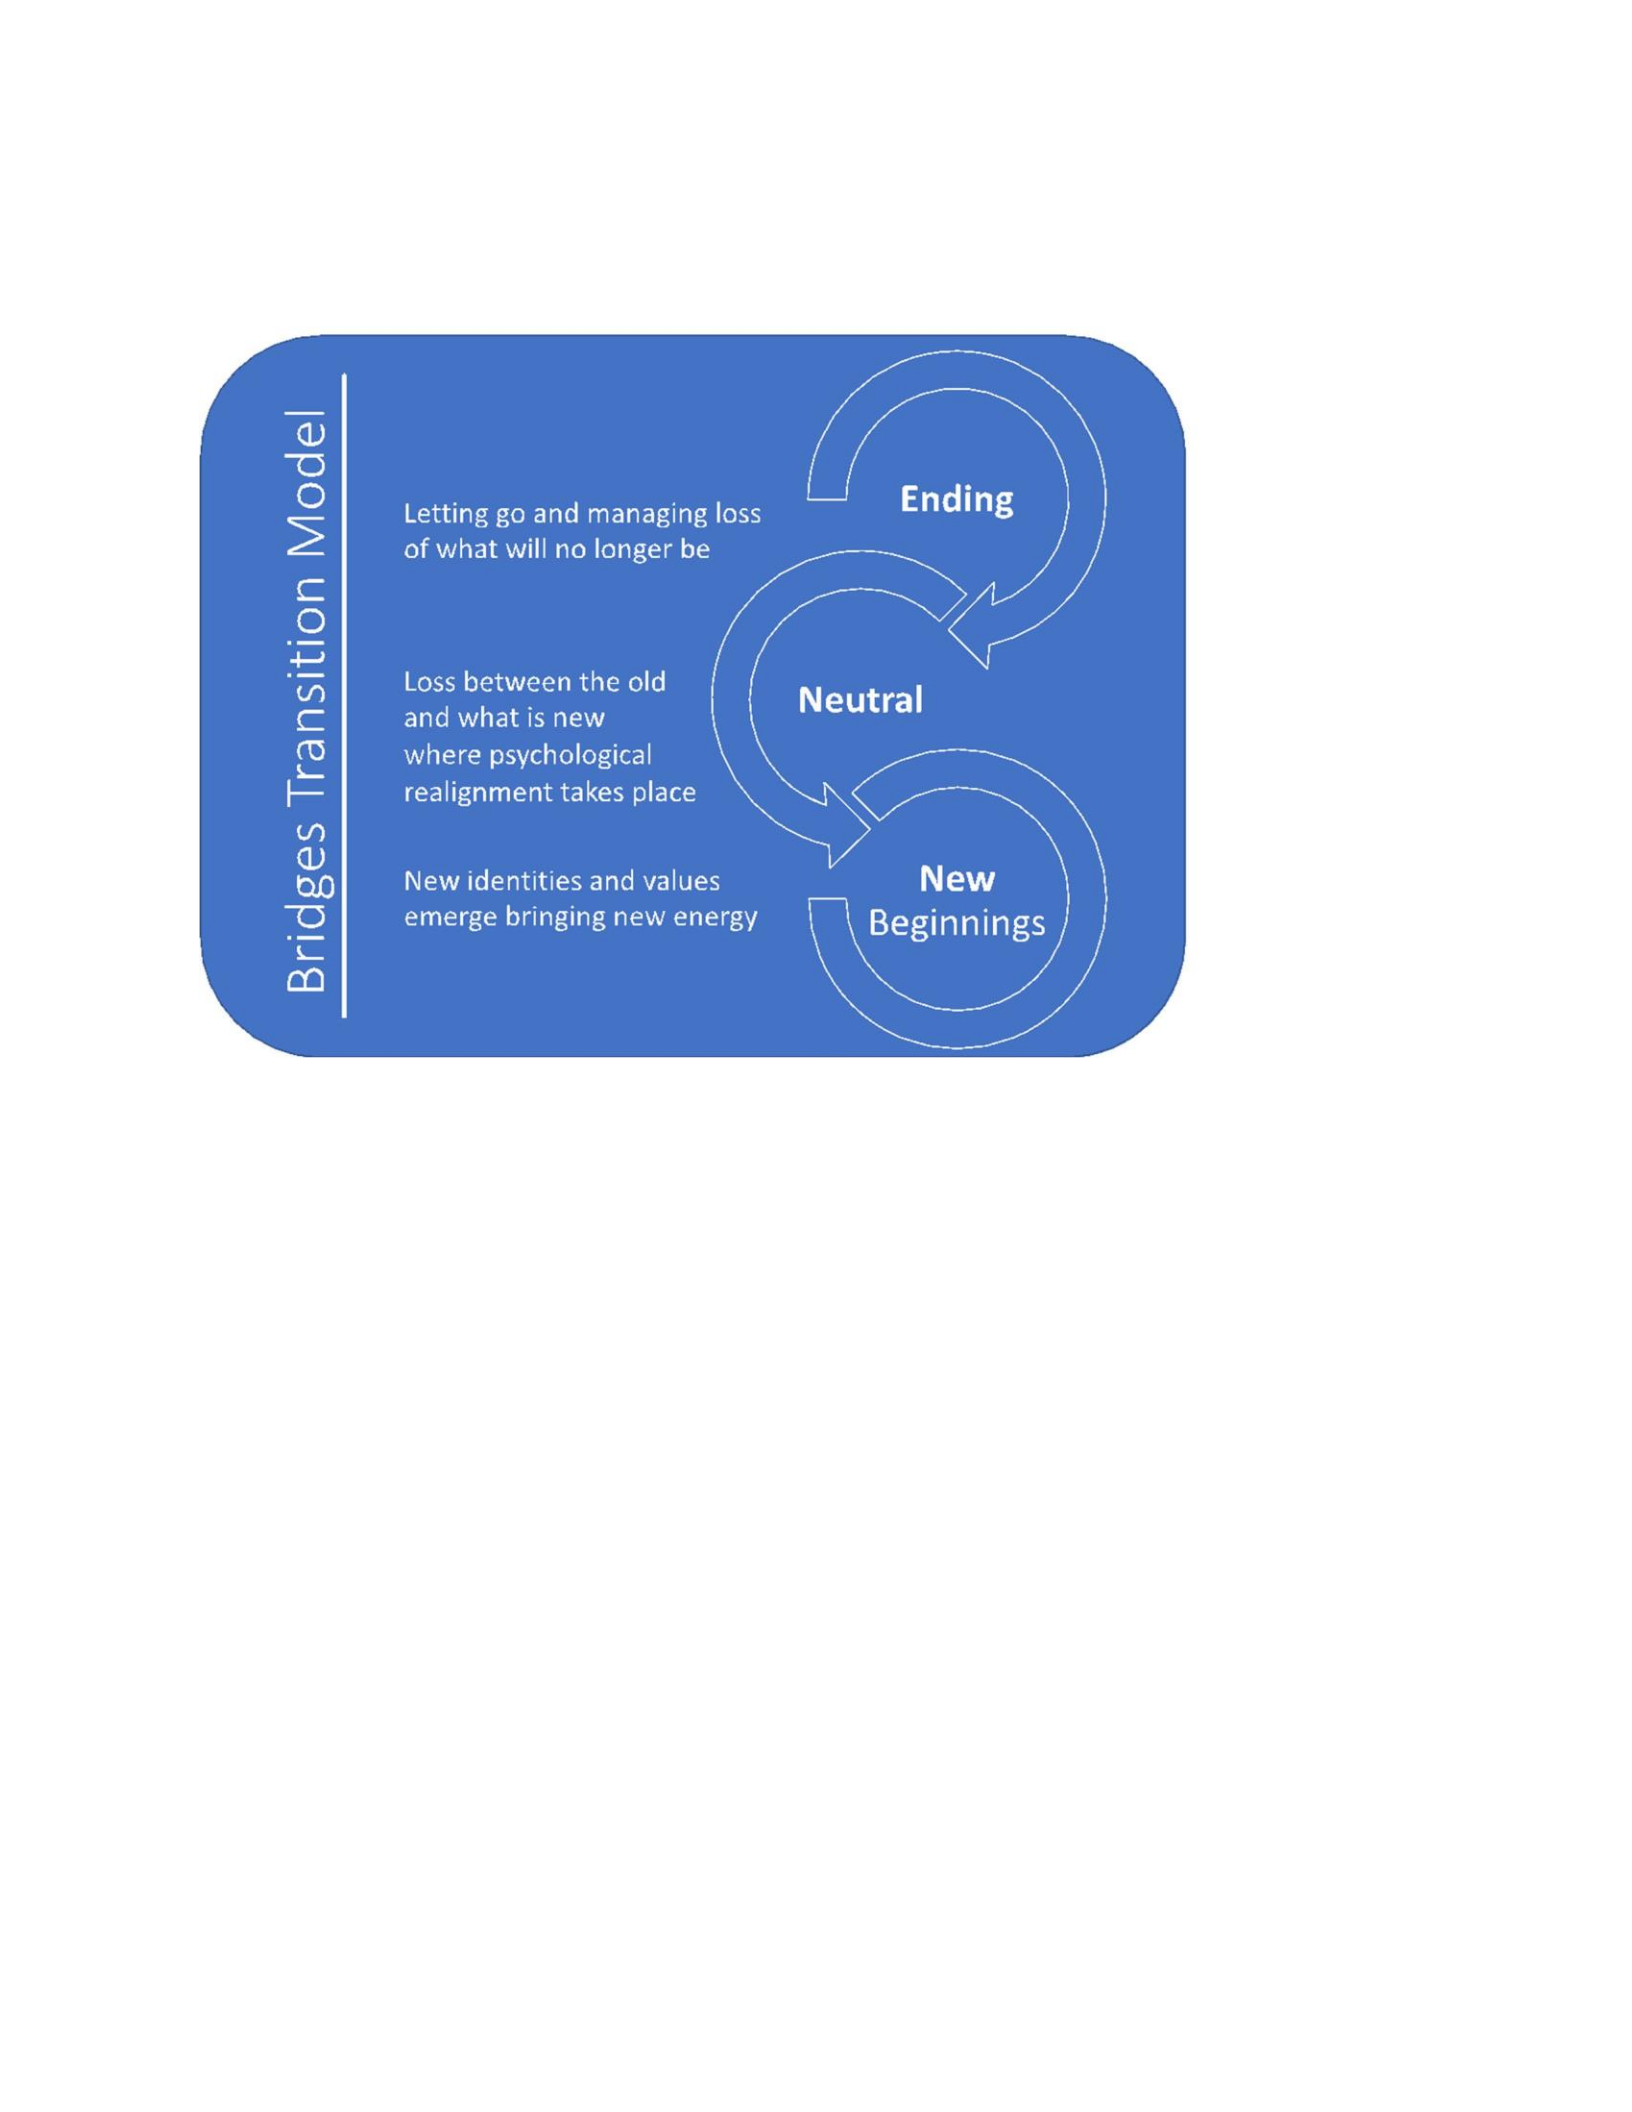
Figure 11
Bridges’ Transition Model
Note. Original figure based on Transitions: Making Sense of Life's Changes, by W. Bridges, 1996,
Nicholas Brealey. Copyright 1996 by W. Bridges.
Schlossberg (1981, 2006, 2011) defines transition as “any event, or non-event, [which]
results in changed relationships, routines, assumptions, and roles” (Anderson et al., 2012, p.
33). This definition embodies the thought that a transition only exists if the person experiencing
it considers it to be a transition. Change occurrences may not be considered a transition if the
individual does not place much meaning or significance on the change. Schlossberg’s Transition
Model (2011) theorizes four domains (4Ss) as diagrammed in Figure 12: (a) situation at the time
of the transition (p. 45); (b) support from people that encourage and the assets that strengthen
the transition; (c) self, the identity of a person related to the level of optimism and dealing with
ambiguity wherein personal demographic factors like age, social economic status, health,
wellness, gender, culture and psychological elements like resiliency, optimism, and spiritual
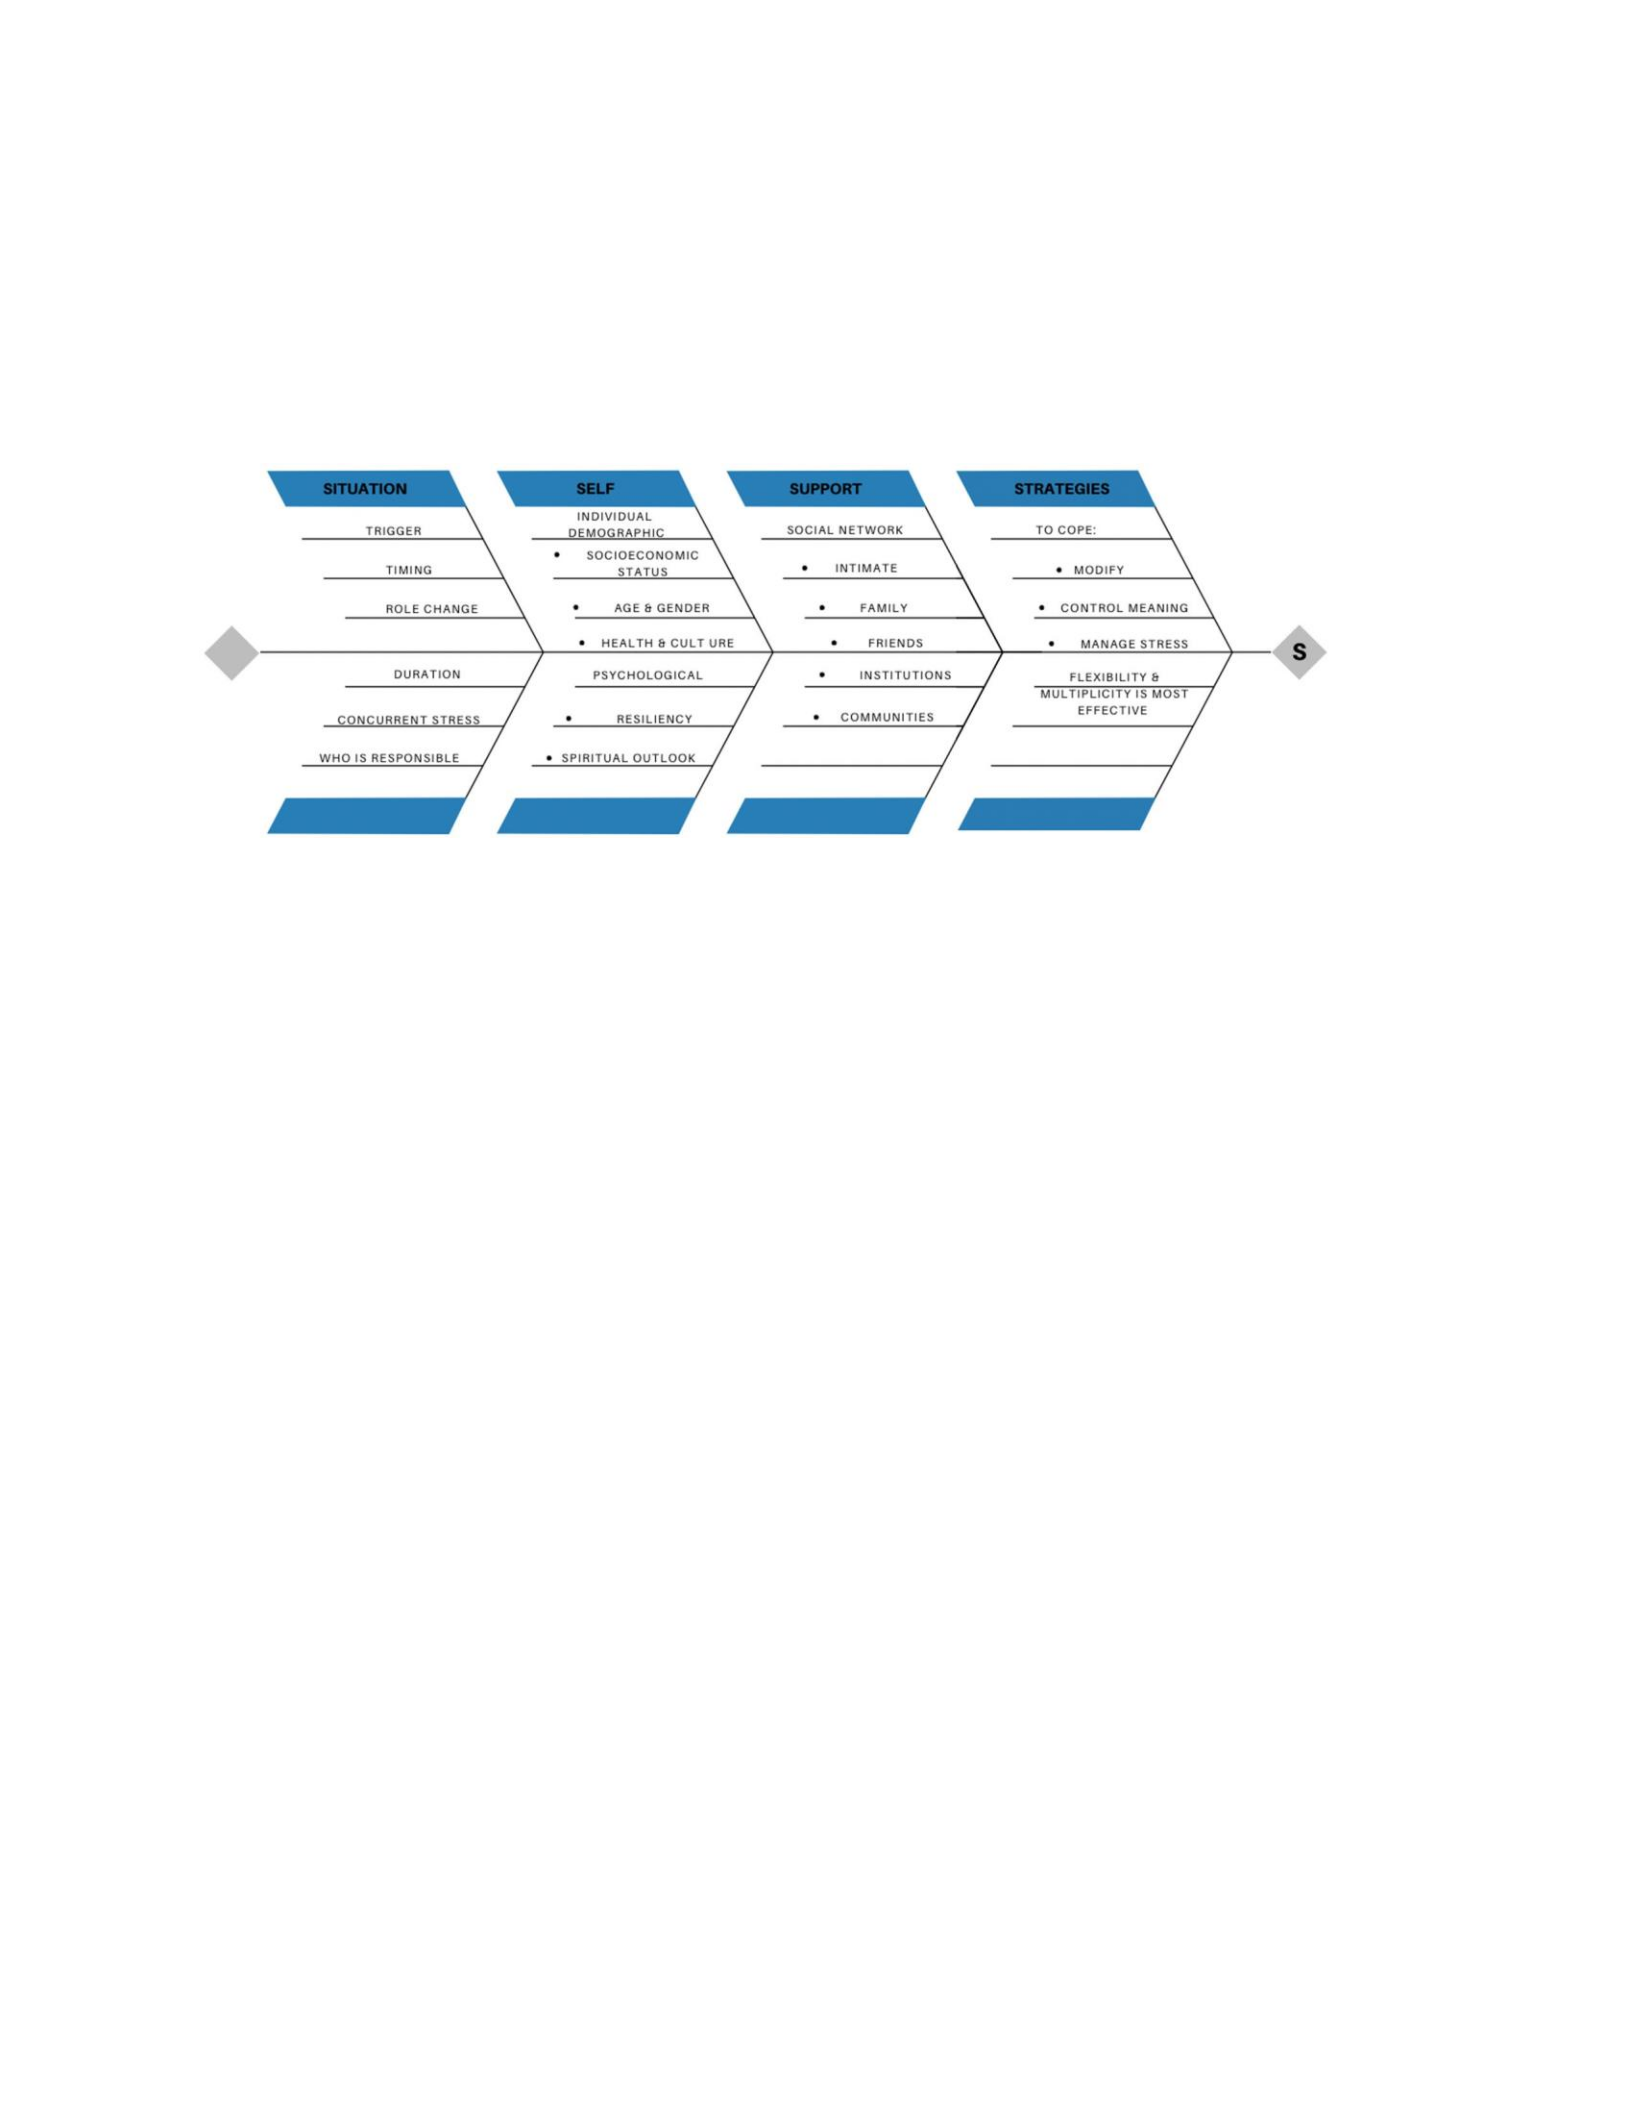
outlook are concurrently taken into consideration; and (d) strategies that present ways and
functions of coping (Anderson et al., 2021).
Figure 12
Schlossberg’s Transition Model
Note. Original figure based on Counseling Adults in Transition: Linking Schlossberg's Theory with
Practice in a Diverse World (5th ed.), by M. Anderson, J. Goodman, and N. Schlossberg, 2021, Springer.
Copyright 2021 by M. Anderson, J. Goodman, and N. Schlossberg.
Succession planning and transition planning outline various phases of leader transfers
that require attention to each phase and stage of the processes (O’Kelley, 2018). If a succession
plan exists it is a pathway of starting a chief executive transition. To make succession work, a
proactive business strategy is essential to ensure qualified, internal people are identified to
assume the next level up leadership positions as vacancies occur (Bonczek & Woodward, 2006;
Carriere et al., 2009; Schmalzried & Fallon, 2007).
Transition planning encompasses candidate selection decisions and steps associated
with the transference of the role from the incumbent CEO to the new CEO. The steps of
successful transition planning engage the organization’s key stakeholders. Concerted efforts are
required to keep the top leadership focused on the business, on value creation for the
organization and routinely identify potential areas of stress so that it is proactively alleviated
(O’Kelley, 2018).
Executive transitions are commonly characterized as high-stakes and high-tension
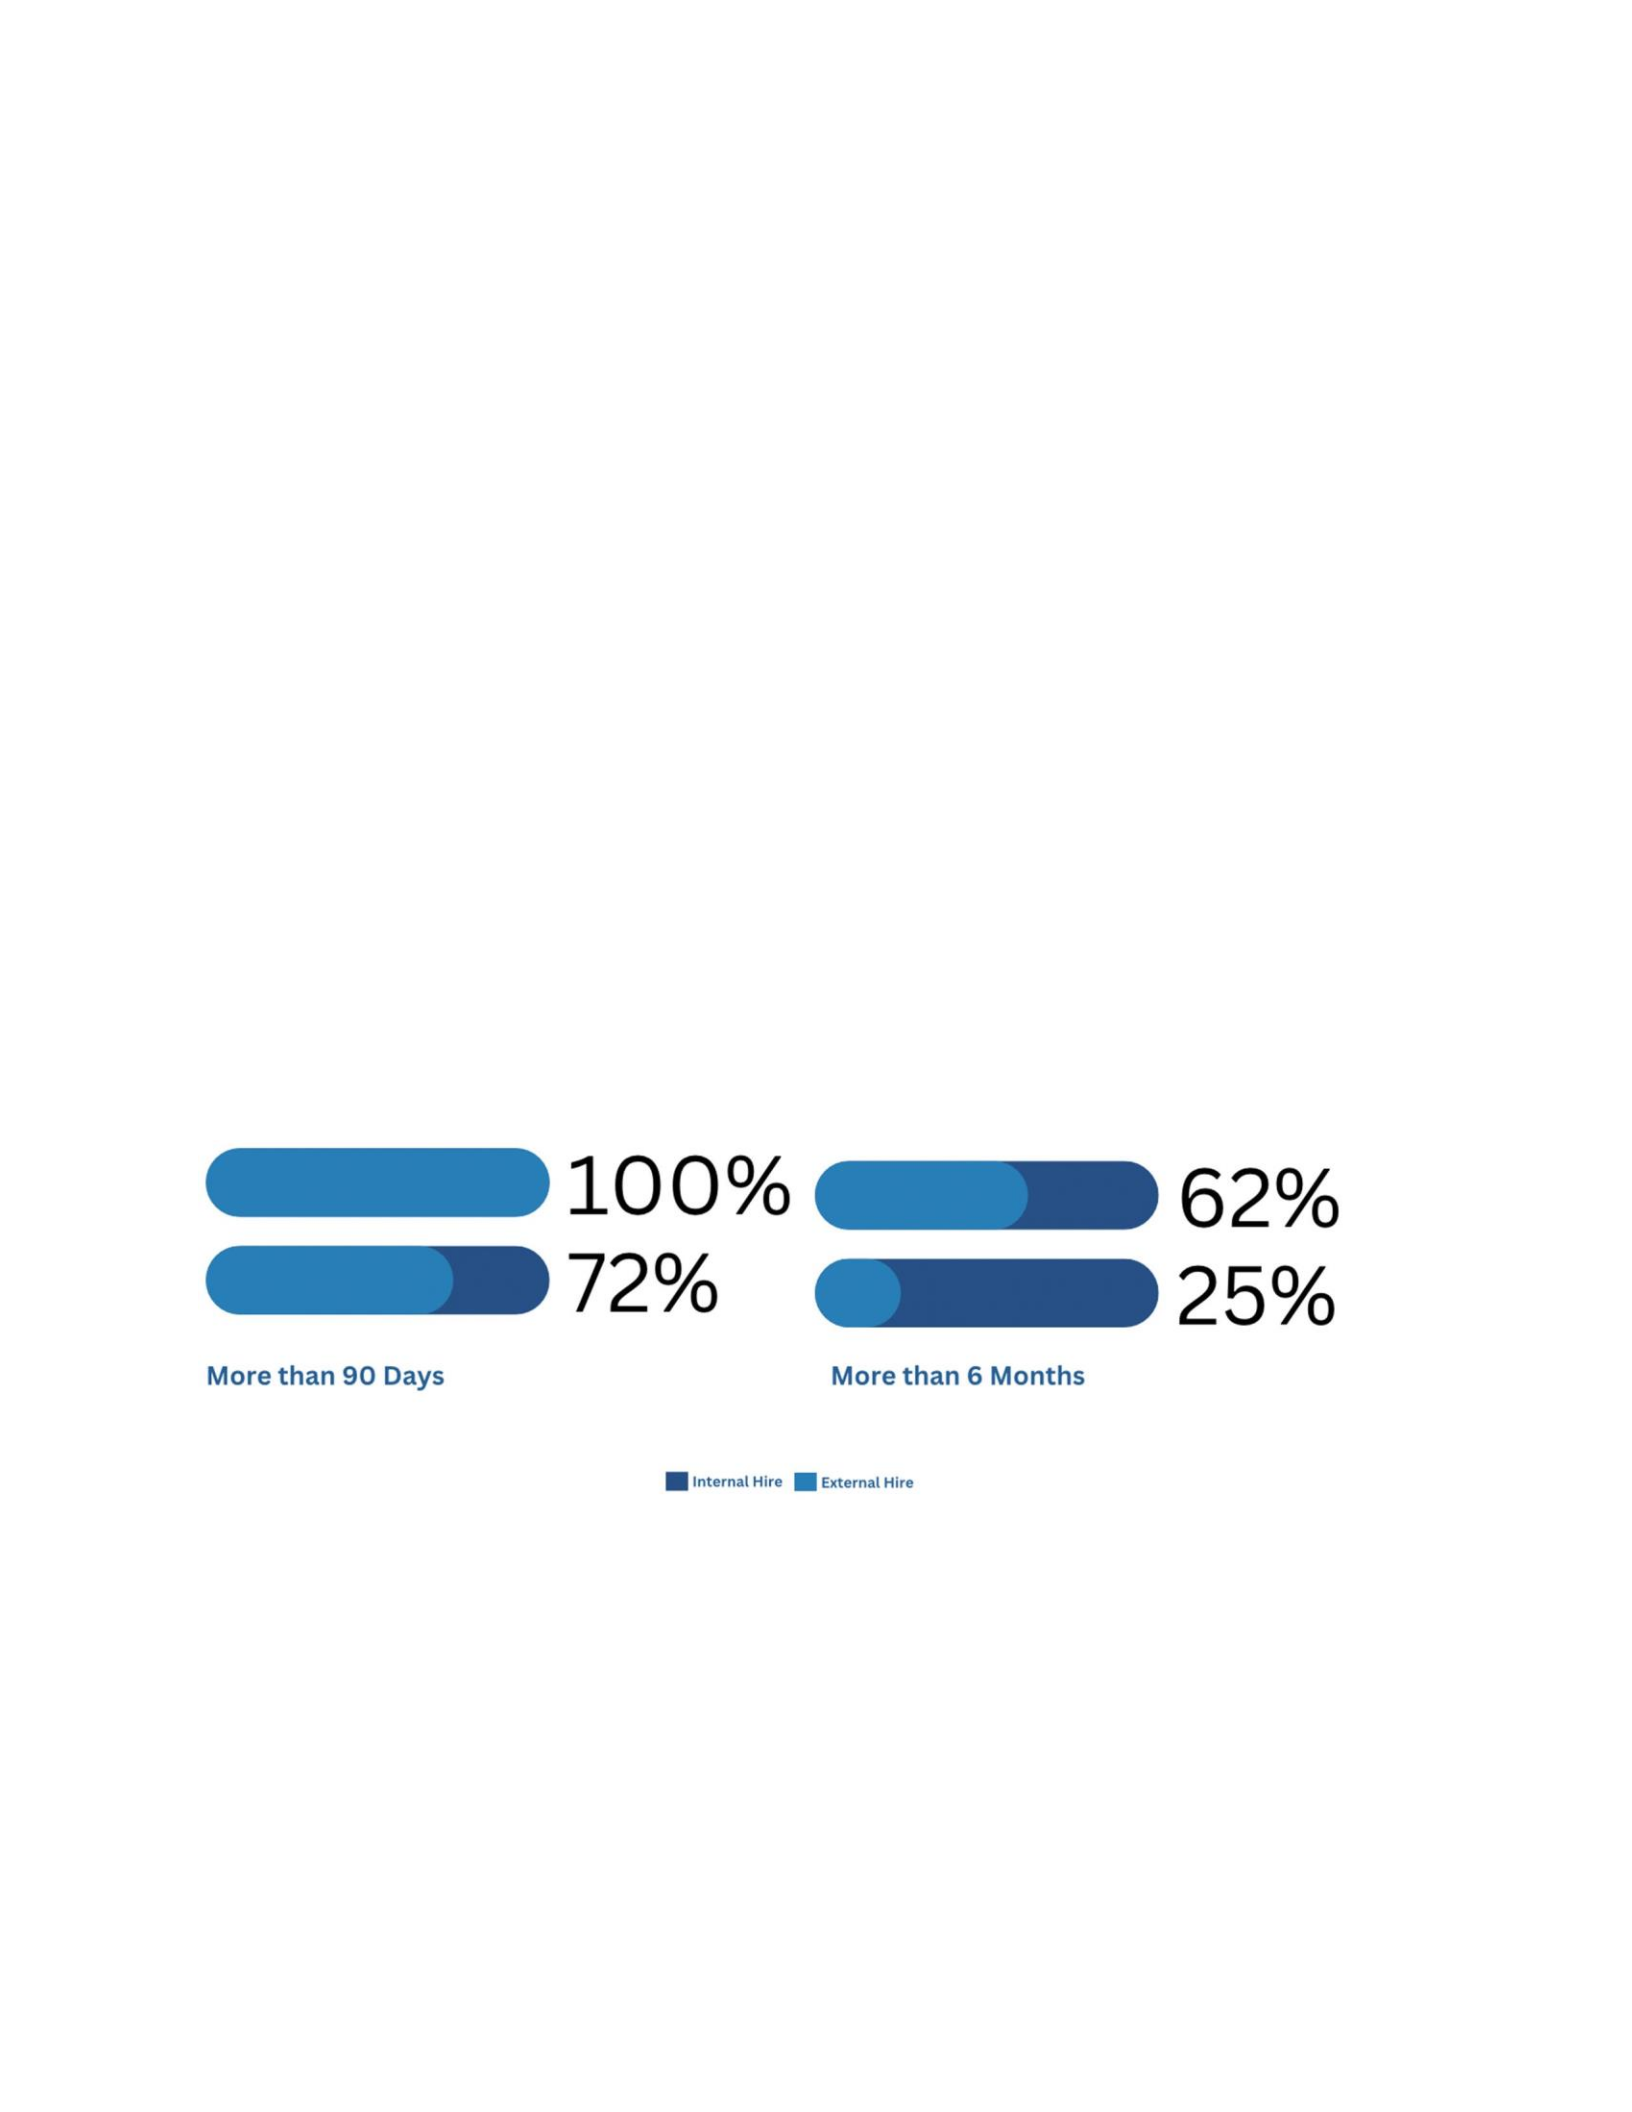
(Dierickx, 2018). Success in a chief executive transition is denoted in several ways. Time in
position is one success measure that is quantitatively highlighted in the literature. According to
the literature, across industries, two to three years is the span of time that is commonly allotted
for new CEOs to demonstrate progress in the financial performance and culture (Ciampa &
Dotlich, 2015; Ciampa & Watkins, 1999; Dworkin & Goldstein, 2014). The notation that new
leaders have 100 days to make the transition is purported as a myth (Gaines-Ross, 2002). This
myth is demystified in Figure 13 presenting a case that transitions both internally placed CEOs
and external hires take longer than 90 days to make a mark on the organization which is in
contrast to Watkins (2003) work entitled The First 90 Days. To achieve success, new leaders
need sufficient time to develop their vision, gain the support of followers, build or rebuild the
team’s capabilities, earn credibility and reinvigorate how the organization does business (see
Figure 14).
Figure 13
Time Needed for Chief Executives to Become Productive
Note. Original figure created based on CEO Capital: A Guide to Building CEO Reputation and
Company Success, by L. Gaines-Ross, 2002, Wiley. Copyright 2002 by L. Gaines-Ross.
Figure 14
Time that Chief Executives Needs for Specific Tasks
Note. Original figure created based on CEO Capital: A Guide to Building CEO Reputation and
Company Success, by L. Gaines-Ross, 2002, Wiley. Copyright 2002 by L. Gaines-Ross.
The duration of CEO transition varies across industries and sectors. Research across
multiple industries is estimated to range between six and nine months (Ciampa & Watkins,
1999; Gabarro, 2007; Gilmore, 1988; Watkins, 2003). While further research studies suggest
transitions may range from 18 months and extend up to three years (Downey, 2002; Levin,
2010; Manderscheid & Ardichvili, 2008). Some researchers opine that the transition period starts
on the first day of the executive's new role (Gabarro, 1987; Gilmore, 1988; Watkins, 2003).
Conversely, other researchers suggest that the transition period begins from the offer
and acceptance stage, happening well in advance of the leader stepping into the new role
(Petrock, 1990). Wiggins (2019) highlights the notion that as soon as a decision is made for an
executive transition, preparations happen for the organization and the leader, which is a
combination of physical and psychological. While arguments exist on when transitions actual
begin, it is undisputed that there is a need to identify elements of how to increase the success
criterion given the high stake of turnover in failed transitions (Dierickx, 2018; Dierickx & McGill,
2007).

Multiple practitioners and authors suggest transition steps for executive transitions. Once
it is determined that a role transition will happen, steps are in order to begin the process which
many authors characterize as stages or phases. Watkins (2003), Watkins (2003) refers to three
phases: preselection, pre-entry, and taking charge. Transition begins at the moment the leader
realizes they are being considered for a new role. The pre-entry phase happens once the leader
has been selected and the official start date launches the taking charge phase (Watkins, 2003).
Gabarro’s (2007) research examined what happens when leaders take on larger new jobs.
The 3-year longitudinal study charted two sets of ten historical case studies of leader
succession. Leaders who assume the role of leadership of large organizations must traverse
through predictable stages to achieve mastery of the job. Specifically, Gabarro’s (1987, 2007)
findings outlined: leaders’ ability to get up to speed took considerably longer than predicted;
successful transitions tracked predictable stages which include two sit-back-and-watch periods
of immersion and refinement; outsiders take longer to take charge than industry insiders; and a
high quality working relationship with a boss dramatically increased the leaders’ likelihood of
success. Most importantly, the research findings showed that transitions take a long time.
Roles in the Transition
Birshan et al. (2016) reported as many as 74% percent of U.S. leaders think they are
unprepared for their new CEO roles (Paese & Wellins, 2015). Over 402 CEOs from 11 different
countries were surveyed admitted they were not fully prepared for the personal and
interpersonal aspects of the transition and the role (Najipoor-Schutte & Patton, 2018). In the
study, 29% of the CEOs reported that their organization appropriately supports new leaders.
Several key constituents are involved in the process of transitioning chief executives.
The process of transition takes on a triangulation approach that includes multiple actors: the
board of directors, the chief human resources officer (CHRO), the incumbent CEO, and the new
CEO on behalf of themself. Boards are the primary actors based on their fiduciary responsibility

of selecting the chief executive. Most leadership transitions the board pays attention to are
narrowly focused exclusively on the search process (Valtas Group, 2019). However, the board
must shepherd the process of the successor’s transition which begins with preparation, followed
by serving as a sounding board and providing feedback and advice (Tuomala & Yeh, 2018).
During preparation, boards seek to understand the requirements for success that will lead to a
clear path on resources and constraints that will need to be navigated for an effective leadership
transition (Najipoor-Schuette & Patton, 2018).
Dierickx and McGill (2007) asserted that the board of directors, senior leaders,
incumbent CEO and the chief human resources officer all play pivotal roles in executive
transition. Whereas the board needs to hold incumbent CEOs accountable to performance and
offer the right amount of oversight and guidance, senior managers must prepare the
organization for the new leader and help the organization’s employees, structure, and processes
adapt to the new leader’s vision. The chief human resources officer is responsible for
coordinating the process and acting as an internal advisor to the process. Finally, the new
leader holds the ultimate responsibility for directing the transition process and achieving
success.
Chief human resources officers play a significant role in ensuring CEO transitions
(Ciampa, 2015). Several areas in which the chief human resources officer can help senior
transitions include serving as an internal advisor to the outgoing and incoming CEO; managing
administrative aspects of the change; facilitating communication between the board and the
senior managers and being instrumental in assisting the new CEO to strengthen ways the
senior team works well together (Ciampa, 2015; Meinert, 2015). There is a gap in the literature
on the instrumental role chief human resources officers play in transitioning CEOs in concert
with the role of the board of directors and the incoming CEO.

The tertiary responsibility of transitioning is the role that the chief executives themselves
play in their transition. In the study of CEOs across 11 countries, 79% agreed with the statement
that they needed to transform themselves as well as the organization. Transitions at the top are
repeatedly reported to fail when major players are unprepared, ignore, or underestimate the
critical complexities of the process. Ciampa and Dotlich (2015) explain the confluence of two
factors that contribute to transition complexity: (a) adjustments required by the key constituents
and interactions between them: the sitting CEO, the board, senior leaders, and the CHRO and
(b) systemic organizational adjustments associated with the transition: cultural, political,
operational and strategical.
Circumstantially, the outgoing CEO and other key constituents would be involved in the
transition of the new CEO. Transition management teams provide a crucial role in the
overarching health of the organization during a time of significant change (Ciampa & Dotlich,
2022). Included in this group are representations from multiple stakeholders that include
perspectives from patients, community partners, frontline leaders, and different dimensional
diverse voices from within the organization’s workforce (Nazemian, 2022; Carriere et al., 2009).
Transition management teams play a crucial role in sustaining the organizational health during
times when there is flux and a need of strong strategies, as well as high talent engagement.
Success and Failure Rates
Research suggests that, in general industry, the first 18 months of the tenure of a new
CEO are a critical period in the transition of a newly appointed chief executive (Nazemian, 2021;
Watkins, 2013; Wiggins, 2019). Ciampa (2005) suggests that approximately 40% of new CEOs
are dismissed within this time. Success is measured by the company’s success (Birshan et al.,
2016). Studies showed nine out of ten leaders who had a successful transition lead their teams
to meet their three-year performance metrics. Indicative of successful transition is longer tenure
or time in position for the CEO. Benefits of successful transitions are baseline productivity levels

that are achieved in a shorter time and the importance of new leaders managing attrition risk
(Nazemian, 2022; L. Wheeler, 2009; S. Wheeler, 2013).
Several researchers noted that the failure rate for executive transition has remained at
40% for more than 15 years (Ciampa & Dotlich, 2015; Fisher, 2012), while Wright et al. (2018)
estimated the success rate as ranging between 54% and 73%. Although these statistics have
remained relatively consistent over the last several years, average tenure of CEOs across all
industries has continued to decline. The more rapid turnover may be the result of the increasing
difficulty of leadership roles due to complex, competitive and resource-constrained
environments (Paese, 2012; Wiggins, 2019).
Participants in the research consisted of 22 board of directors who combined served on
a total of 135 boards that ranged an average of 6.1 per interviewee with active involvement in 97
CEO successions. Of the 97 CEOs, the board member characterized the success rate as 67%
which represented a successful CEO succession decision by the board. On the other hand, 28%
of CEO succession decisions failed with another 6% tilting toward failure (Wright et al., 2018).
Research conducted by Development Dimensions International (Paese, 2021) concluded based
on a meta-analysis of transition studies that external executive hires have a lower success rate
(53%) compared to executives promoted internally (65%).
The Effect of Executive Transitions
CEO transitions have been described as trigger events that ignite other organizational or
individual changes (Bridges, 1996; Schlossberg, 2011). Successful executive transitions
resulted in lower risk of attrition, higher discretionary contribution to the work, greater revenue,
and profit. Results achieved within the first 18 months is one measure of success. Ciampa
(2021) points out that success is demonstrated through a substantial critical mass of followers
who have accepted the leader. Additionally, the future career trajectory of the CEO with the

likelihood of being considered for greater promotions externally after the completion of one or
more successful transitions (Nazemian, 2019).
In contrast, CEO transition failure has far-reaching implications that adversely affect
hospitals and their communities, such as compromised community outreach programs,
development of new services, physician recruitment, and maintenance of clinical care provider
relations (Khaliq et al., 2006). Further, failed CEO transitions thwarted strategic planning,
negatively impacted hospital culture, and diminished employee morale (Murphy & Zimmerman,
1993). However, there are opposing positions that CEO turnover has a positive impact on
financial performance, staff engagement, and board relations (Khaliq et al., 2006; Murphy &
Zimmerman, 1993; Wilson et al., 2000). Unsuccessful transitions also can give competitors the
opportunity to seize a recruiting advantage of people unsettled by the circumstances.
Competitors frequently sought to recruit the hospitals’ physicians, attract its patients, and recruit
its key employees between 39 to 45% of the time when a chief executive transition occurred
(Khaliq et al., 2006; Nazemian, 2021). Bharucha and Dial (2013) found in their research on
executive transition that direct reports were more likely to leave the organization or be
disengaged following executive transition.
Chief executive transition also tends to create a ripple effect through the rest of the
executive team. Khaliq et al. (2006) found in their study of more than 2,100 hospital CEOs that
executive team turnover was elevated within one year of the chief executive transition, with 77%
of chief medical officers, 52% of chief operating officers, and more than one third of chief
executives in finance, human resource, and information systems leaving the organization.
Multiple transitions at the chief executive level ignite downstream complexities of business
operations, additional leader exits or leader disengagement that transcends to the workforce
(Khaliq et al., 2006). The Conference Board’s (2012) study magnifies impact of a decline in
productivity of a struggling executive transition, reporting a statistically significant difference

among direct reports that work with a high-performing and well transitioned executive. The
findings suggested that organizations that experienced struggling transitioning executives
performed, on average, 15% lower than organizations with successful executive transitions.
Contributors to Transition Outcomes
Wright et al. (2018) researched the phenomenon of factors that affect CEO succession.
Paese (2021) presupposed that the underlying factors of chief executives' transition failure are
not a new phenomenon. Complexity is inherent in a leadership transition because it is not a
singular transition. The process is multifaceted with various moving parts that exist through
interdependent steps with one-third of the senior executives leaving their positions within 18
months of the appointment (Ciampa & Dotlich, 2015; Williams, 2010).
A second perspective is that executives are unaware of the undermining factors that
impact failed transitions. Boards have forced CEO departures at the rate of 46% which impacts
the organization’s financial and human capital costs (Dierickx & McGill, 2007; Fatemi, 2016;
Tonello et al., 2009). The board, chief executive team members, and the CEO themselves are
surprised by the failed transition (Paese, 2021). Nazemian (2022) asserted that the new leader’s
demeanor during onboarding is crucial, as people watch what the new leader pays attention to
as employees seek understanding about what the new leader values.
Examination of external versus internal executive transitions provides additional insights
about the causes of transition failure. Externally recruited executives face greater challenges in
transitioning into the chief role primarily due to the lack of understanding of the organization’s
culture and need to establish critical relationships (Charan et al., 2011; Ciampa & Watkins,1999;
Dai et al., 2011; Dutton, 2010; Manderscheid & Harrower, 2016; Watkins, 2009; Wiggins, 2019;
Zhang, 2008). Nazemian (2021) grouped the top contributing factors for executive transition
failure into three categories: politics, people, and culture. Regarding politics, new executives
may fail to properly read nuanced political situations that enable building alliances and essential

relationships. Regarding people, incoming executives may fail to build collaborative teamwork
with staff and peers and further may miscalculate the willingness or the capacity of the people
they inherit to abandon deep-rooted habits and behaviors. Regarding culture, new executives
may fail to understand and modify the cultural norms and practices or fail to realize the cultural
changes their strategic and operational agendas require.
Schein (2010) asserts that organizational culture is a substantial feature of any company
that emerges and is reinforced by long-term social learning about the environment, needed
behaviors, and the purposes of the organization (Gilmore, 2003; Schein, 1985, 2010; Tierney,
1986). Accordingly, culture tends to be resistant to leaders’ intentional manipulation to establish
a particular climate. Moreover, the boards of directors that select and install new chief
executives tend to underestimate the role of culture in strategy execution and the time that is
needed for any culture change (Carucci, 2017; Nazemian, 2021). Nazemian (2021) advised that
it can take two to three years to realize the impact of the new CEO’s decisions on financial
results. He further asserted that culture is one of the most crucial elements of successful
organizations and that researchers should examine culture as an overarching cause of
executive transition failure.
Internal executive transitions as a result of a promotion share some of the same critical
success factors as the external hire. However, there are some elements that are uniquely and
distinctively different in the internal promotion. Managing previous colleagues who were laterally
equivalent on the organizational hierarchical ladder and have not subscribed to the newly
minted leader’s ascension (Charan et al., 2011). There is data that purports that it is more
challenging for an internal promotion to manage existing relationships (Charan et al., 2011;
Wiggins, 2019).
Successful transitions at the executive level would create substantial benefits to any
organization (Dai et al., 2011; Watkins, 2019). Therefore, increasing success factors and

mitigation or minimization of obstacles is an important focus for all key stakeholders in the
transition process. People’s perspective of who or what is responsible for the transition affects
their appraisal of themselves, the environment and the overarching. Individuals' attributions
about the situation and about self are elements of consideration when assessing transitions
success (Anderson et al., 2021).
A concept that predicts how a person will negotiate transitions is self-efficacy. Bandura
(1977, 1986, 1997) coined the term self-efficacy to describe a belief that people own their life
and have an impact on their environment. The theory goes further to suggest that it is an
individual's belief they have the capacity to implement behaviors necessary to generate specific
performance attainments. Self-efficacy reflects a person’s confidence in their ability to exert
control over their behavior, motivation and social environment (Bandura, 1977). In other words,
self-efficacy in the context of transitions provides an individual with confidence and the capacity
to fix their own actions. Outcome expectations is another theory addressed by Bandura (1986)
that is defined as anticipated consequences, either positive or negative, as a result of engaging
in self-directed career and organizational behaviors to accomplish goals (Anderson et al., 2021;
Bandura, 1986, 2001; Fasbender, 2019; Lent, 2013; Lopez et al., 2015). Self-efficacy proposes
a construct to explain behaviors in the face of obstacles (Anderson et al., 2021).
Self-awareness is another dimensionality of the considerations of successful transition
outcomes. Silvia & O’Brien (2004) describe self-awareness as an individual’s ability to
selfevaluate by turning attention on self in a focused way. Research shows that self-awareness
in leadership roles is a critical key factor of high performance as well as an indicator of a
duration of career success (Church, 1997; Sala, 2003). A growing body of empirical research
postulates an association between self-awareness and successful leadership (Ashley et al.,
2012).

Higgs and Rowland (2010) researched reasons change fails in organizations. The
research focused on illuminating the broad contextual factors affiliated with the change process.
A key consideration on change implementation hinges on the leaders’ understanding and
recognition that they act within the complexity of organizational systems (Higgs & Rowland,
2010). Interviews with leaders from 33 organizations in a leadership role that were involved in
organizational change framed the researchers’ premises on self-awareness associated with
success or failure of a change imperative. Leaders’ lack of knowledge of systemic issues,
consciously or unconsciously, reinforces nuanced behaviors and patterns that impaired the
implementation of change or reinforce systemic attributes that sideline progress (Goodwin,
1978; Higgs & Rowland, 2010; Higgs & Rowland, 2005; Rowland & Higgs, 2008). Analyses of
the data indicated two divergent outcomes. Leaders’ that focused more on their individual needs
were blind to organizational systems resulting in limited success of change interventions.
Conversely, leaders who exhibited behaviors that amplified high degrees of self-awareness,
ability to be present in the moment and sustain relatedness to the overarching purpose of the
change, were involved in successful change efforts. The research supports the complex view of
change that requires an understanding of the underlying systemic structures (Higgs & Rowland,
2010; Senge, 1990; Weick, 1995).
Special Considerations in Hospital Systems
Every organization experience leadership changes that may be planned or unplanned.
The pace of CEO transitions at large U.S. hospitals shows an uptick from previously recorded
annual exits that range between 13% to 18% per year, with average hospital CEO tenure of five
years and annual turnover statistics averaging 17% since 2012 (ACHE, 2022b). Top executive
turnover has major implications for any organization; yet, the circumstances and impacts of
hospital CEO transitions have not been fully investigated as a catalytic change for the
organization (Khaliq et al., 2006). This is a significant omission in research, as large hospital

system CEOs play a unique role of leading the mission, organizational culture of a highly
specialized workforce.
While organizations are known to have layers of complexity that must be considered in
CEO transitions (Watkins, 2009), large teaching hospital systems’ tripartite mission makes
executive transitions unique because of the revolution that is underway that is fundamentally
changing how academic medical centers operate as well as how they are being led (Enders &
Conroy, 2014). CEOs of large health systems will transition during a time of industry disruption,
financial constraints, changing economic dynamics, marketplace consolidation, and a keen
focus on lower cost structures while improving patient quality require chief executives to
consider new operating models for academic medicine (AAMC, 2021). Every aspect of
academic medical centers are undergoing transformation: how care is delivered, new ways of
educating students and residents in new modalities, how the research enterprise is organized
and funded, and how the tripartite missions come together in a new way that adds value to the
system (Enders & Conroy, 2014).
Physicians’ and clinical teams’ dissatisfaction with the way they are managed lies in the
misalignment of their individual orientation of how they were trained which contrast with the
current demands of healthcare systems (Edwards et al, 2002). Hospital CEOs who are not from
a clinical background or are not medically qualified are more prevalent in running large health
systems creating the potential for discord with medical practitioners who need to be involved in
the functioning of a hospital (Chadi, 2009). An omnipresent duality prevails between clinical
practitioners and CEOs: physicians do not want to engage with CEOs who are not
understanding of their reality of patient care (Chadi, 2009; Clark & Morgan, 2007; Dowton,
2004).
Literature on leadership transitions has increased over the last decade, with most
publications coming from search firms or consulting organizations (Manderscheid & Harrower,

2016). Levin (2010) highlighted that the reality of leader transitions in practice outpaced
research that is qualitatively based on empirical findings to define critical factors that
differentiate between success and failure. The dearth of research on chief executive transitions
in large complex systems indicates the need to better understand how the success of these
pivotal events may be enhanced within healthcare organizations. In particular, the growing
complexity of large hospital systems’ environments and accelerating pace of change within the
healthcare industry indicate that additional research is required. The next section examines
research on the complex environments hospital systems are facing. Namely, their environments
are marked by multidimensional change that exerts specific pressures on these organizations
and their leaders.
Multidimensional Change and Executive Transition in Hospital Systems
Multidimensionality is a relevant description of the confluence of aspects that leaders are
addressing. Multidimensionality is defined as “the quality of a construct that cannot be
adequately described by measuring a single trait or attribute” (“Multidimensionality,” 2023). The
adjective multidimensional describes anything with many different parts, dimensions or aspects.
Multifactorial aspects of change are occurring in healthcare concurrently with executive
transitions: clinical and workforce challenges, supply chain availability and financial buoyancy,
as aforementioned. Transitions and organizational change are constant dimensions for
healthcare systems. The literature postulates strategies for managing successful change as
environmental factors continue imposing volatility on businesses (Nelson & Pilot, 2015). For the
purpose of this study, multidimensionality was examined in the context of organizational culture
and change during executive transitioning. Research indicates that an entire industry can
experience the impact of decisions when one major organization’s leadership establishes policy
or practice changes (Derenoncourt et al., 2021, 2022; National Bureau of Economic Research,
2021).

Large hospitals are facing significant pressures that create workforce and organizational
challenges leading to various types of multidimensional change (Derse & Bateman, 2021). A
survey of 85 US healthcare leaders predicted the outlook of the healthcare workplace in 2023.
Of the respondents 66% worked in the C-suite or on the Board of Directors, 22% were senior
Vice Presidents and 12% were Vice Presidents. Findings from the survey showed that 52%
predict labor and workforce issues will be their biggest challenge over the next 12 months. In
addition, 24% of respondents are considering layoffs in the next 12 months with 13% currently in
the process of workforce reductions (Bean, 2020). The literature highlights the environment in
which healthcare is operating is rapidly changing (Bean, 2020; Swanson, 2022). In this regard,
every healthcare system should assess the impact of anticipated changes to its external labor
market in concert with the effect on people and patients (Derse & Bateman, 2021).
Hospital systems face indelible paradigm shifts in doing things differently from how they
have done for years. Shifts in the economy and the workforce continue to add complexities to
leadership challenges in leading academic hospital systems (Lantz, 2008; Weintraub & McKee,
2019; Wheatley, 2010). As turnover among healthcare executives continues to reach new levels,
the dilemma of continued disruption will exacerbate within the industry and hinder hospitals’
organizational performance (Wheatley, 2010).
Despite organizational change research existing for more than 70 years, there is minimal
knowledge about how multidimensional change factors intersect or co-exist, leaving leaders with
experimentation to build experience over time (Donald, 2019b). Milella et al. (2021) asserts, the
healthcare industry is experiencing accelerated multidimensional change rendering an urgent
need for organizational change. Each transition disrupts business as usual. Simultaneous with
turnover rates for hospital CEOs increasing, innovative approaches to caring for patients and
workforce challenges have hoisted change. Change accelerators serve as transitions that push

the limits on people’s comfort zones. Managed properly, change can benefit organizations
(Milella et al., 2021).
Change in an organization is disruptive and creates uncertainty among its members
(Khaw et al., 2022; Martin, 2013). Regardless of the change endeavor in contemporary
organizations, the prevalence of resistance is substantial. Khaw et al. (2022) asserted that
uncertainty creates multiple concerns, such as fear about what is happening, and unchecked
uncertainty nurtures resistance (Ford et al., 2021). Even if changes are good, research suggests
people do not like feeling voiceless, incompetent, or anxious (Kotter, 1995; Kotter & Cohen,
2012).
As routine practices and protocols change, the existing knowledge and skills undermine
people’s ability to perform confidently and succeed (Bolman & Deal, 2017). Congruity affords
people to experience life as “orderly, predictable, familiar, and safe” (Bailey & Raelin, 2010,
2015). Thereby, it stands to reason that change makes people question their orderly routines,
causing them to feel threatened (Bailey & Raelin, 2010; Martin, 2013). Change undermines
existing structural constructs, creating ambiguity, confusion, and distrust (Bolman & Deal, 2017).
When this occurs, people question what is expected of them or what they can expect from other
members. Change at the top, or in general, by some members means the elimination of the
status quo causing individuals and groups to lose their power in an organization (Bolman &
Deal, 2017; Martin, 2013; Watkins, 2013). In this regard, members work in contradiction of
change to ensure they maintain their power.
Multidimensional organizational culture change during chief executive transitions affects
the positive work environment that promotes employee experiences, engagement, and
productivity. In healthcare, the multidimensional change that occurs during chief executives’
transition affects people's lives and livelihoods. Gone undetected or managed, chief executive

transitions that affect the livelihood of people and the way they work ultimately transcends to
patient care (Bailey & Raelin, 2010; Gebreyes et al., 2021; Martin, 2013; Swanson, 2022).
In the face of rapid disruptions resulting from multidimensional change, organizations’
chief executives are required to appropriately respond in ways that address the new realities.
CEOs and their teams are sought out to make sense of the changing realities, to understand the
new workforce patterns, clarify the organization’s purpose, assess strategy to purpose and
galvanize people to execute the strategy. At the heart of the matter is the chief executives’ role
in leading a learning organization that is agile to change. Senge (1994), introduces an analysis
of systems thinking in the seminal book, The Fifth Discipline - The Art and Practice of Learning
Organization. In this work, Senge (1994) presents disciplines of a learning organization in five
categories: personal mastery, mental models, building shared vision, team learning, systems
thinking. Theories that align with the topic of chief executive transitions during
multidimensionality are grounded in constructivist theory.
Summary
Healthcare is the fastest growing industry in the United States and globally (Bureau of
Labor Statistics, 2022). Demand for healthcare services is anticipated to grow in the coming
years, triggering growth in the sector (Swanson, 2022). Furthermore, the increasing complexity
of regulatory and global environments means that healthcare systems will face ongoing
pressures for change that, often, is multidimensional in nature (Derenoncourt et al., 2021, 2022).
These significant changes can herald the need for executive transition. At other times,
installation of new executives can be followed by the designing and implementation of
multidimensional change efforts. While executive transition in general is fraught with challenge
and failure rates are high, executive transition during conditions of multidimensional change are
particularly challenging.

Furthermore, frameworks for enhancing the success of executive transition in large
hospital systems are lacking. This gap is concerning, considering the instrumental and
expanding role of hospital systems in sustaining national health and wellbeing. The present
study aspires to help fill this gap in research by identifying the most important organizational
practices, people and critical processes for chief executive transitions at large hospital systems
during times of significant multidimensional change.
The lists below present 75 organizational practices related to executive transition that
were identified in extant literature and should be carried out by the board of directors, the search
firm, the CHRO, the departing CEO, the incoming CEO, the executive team, senior managers,
and by multiple stakeholders in collaboration (Bond & Naughton, 2011; Ciampa, 2015; Gaines-
Ross, 2002; Jones et al., 2009; Lancaster et al., 2020; Najipoor-Schuette & Patton, 2018;
Tuomala & Yeh, 2018). These behaviors concern activities to carry out in planning the transition,
sourcing candidates, screening the opportunity, preparing the organization for the new CEO,
and orienting the new CEO and the organization to each other. The next chapter describes the
methods that were used in the present study.
Activities to be carried out by the board of directors include:
• The board of directors provides sufficient oversight of the new CEO (Lancaster et al., 2020;
Najipoor-Schuette & Patton, 2018; Tuomala & Yeh, 2018).
• The board of directors identifies the needed competencies in a new CEO (Lancaster et al.,
2020; Najipoor-Schuette & Patton, 2018; Tuomala & Yeh, 2018).
63
Assure the board of directors remains involved as a sounding board and advisor to
the incoming CEO (Lancaster et al., 2020; Najipoor-Schuette & Patton, 2018).
The board allows incoming CEOs more than 3 months and up to 3 years to develop
their vision and have an impact (Gaines-Ross, 2002; Lancaster et al., 2020;
Tuomala & Yeh, 2018).
• The board establishes a CEO search committee (Lancaster et al., 2020;
NajipoorSchuette & Patton, 2018; Tuomala & Yeh, 2018).
• The board finds the executive search firm (Lancaster et al., 2020; Najipoor-Schuette
& Patton, 2018; Tuomala & Yeh, 2018).
• The board develops accurate leadership and system profiles for the search
(Lancaster et al., 2020; Najipoor-Schuette & Patton (2018).
• The board address the interests of internal candidates (Lancaster et al., 2020;
Najipoor-Schuette & Patton, 2018; Tuomala & Yeh, 2018).
• The board deliberates and decides on a new successor (Lancaster et al., 2020;
Najipoor-Schuette & Patton, 2018; Tuomala & Yeh, 2018).
• The board selects a search firm that fits the organizational culture (Lancaster et al.,
2020; Najipoor-Schuette & Patton, 2018; Tuomala & Yeh, 2018).
• The board selects a search firm that understands and respects the organization’s
mission and vision (Lancaster et al., 2020; Najipoor-Schuette & Patton, 2018).
• The board decides whether internal candidates will be considered as possible
successors and communicates this decision (Lancaster et al., 2020;
NajipoorSchuette & Patton, 2018).
• The search committee keeps the board engaged and informed throughout the
process of finding possible succession candidates (Lancaster et al., 2020;
NajipoorSchuette & Patton, 2018).
• The board should prohibit the incoming CEO from sitting on community boards for at
least two years so they focus on the new role (Lancaster et al., 2020).
The chief human resources officer carries out the following activities:
• Chief human resources officer should create a transition management team to
monitor and enhance organizational health during the change (Ciampa, 2015;
Lancaster et al., 2020).
64
• Chief human resources officer should include patients, community partners, frontline
leaders, and diverse voices from the organization workforce in the transition
management team (Ciampa, 2015; Lancaster et al., 2020).
• Chief human resources officer should identify and address organization culture
issues during the transition (Ciampa, 2015; Lancaster et al., 2020).
The chief human resources officer serves as an internal advisor to the outgoing
CEO (Ciampa, 2015; Lancaster et al., 2020).
The chief human resources officer serves as an internal advisor to the incoming
CEO (Ciampa, 2015; Lancaster et al., 2020).
• The chief human resources officer manages administrative aspects of the change
(Ciampa, 2015; Lancaster et al., 2020).
• The chief human resources officer facilitates communication between the board and
the senior managers (Ciampa, 2015; Lancaster et al., 2020).
• The chief human resources officer assists the new CEO to improve functioning of
the senior team (Ciampa, 2015; Lancaster et al., 2020).
• The chief human resources officer coordinates the transition process (Ciampa,
2015; Lancaster et al., 2020).
• The chief human resources officer acts as an internal advisor to the process
(Ciampa, 2015; Lancaster et al., 2020).
• Chief human resources officer supports incoming CEO in learning new perspectives
(Ciampa, 2015; Lancaster et al., 2020).
• Chief human resources officer supports incoming CEO in adopting new behaviors
(Ciampa, 2015; Lancaster et al., 2020).
• Chief human resources officer provides support for incoming CEO’s experiences of
anxiety, stress, or alienation (Ciampa, 2015; Lancaster et al., 2020).
• Chief human resources officer implements a succession planning framework for
executives and mid-level leaders (Ciampa, 2015; Lancaster et al., 2020).
• Chief human resources officer creates leadership and system profiles for the new
CEO based on the organization’s culture, market strengths, and opportunities
(Ciampa, 2015; Lancaster et al., 2020).
65
• The chief human resources officer conducts a formal review of the new CEO’s
performance within their first 6 months on the job (Ciampa, 2015; Lancaster et al.,
2020)..
• Administrative team members focus on being open to different and new ways of
doing things (Lancaster et al., 2020).
• Each executive team member should create a description of their division, direct
reports, recent accomplishments, and current projects to share with the transitioning
CEO (Lancaster et al., 2020).
Multiple stakeholders carry out the following activities:
• Administrative staff and outgoing CEO create a list of suggested “introductory tasks
for the new CEO to consider during the first 90 days on the job” (Lancaster et al.,
2020).
Before the transition, the outgoing CEO spends time with incoming CEO to
introduce them to the local community and key stakeholders (Lancaster et al.,
2020).
The incoming and outgoing CEO should work together regarding transition timing
and priming the organization for the new CEO’s successful entry (Lancaster et al.,
2020).
• The incoming and outgoing CEO should be in regular communication leading up to
the transition (Lancaster et al., 2020).
The incoming chief executive carries out the following activities:
• Administrative staff and outgoing CEO create a list of suggested “introductory tasks
for the new CEO to consider during the first 90 days on the job” (Lancaster et al.,
2020).
• The incoming CEO focuses on getting to know the organization’s people early in the
transition (Jones et al., 2009; Lancaster et al., 2020).
• The incoming CEO meets one-on-one with administrative staff and physician
leaders to get to know them (Bond & Naughton, 2011; Jones et al., 2009; Lancaster
et al., 2020).
• The incoming CEO holds group meetings with organizational directors (Bond &
Naughton, 2011; Jones et al., 2009; Lancaster et al., 2020).
66
• The incoming CEO should classify the organizational projects and initiatives as, a)
continue,, b) pause, or, c) gather more information (Bond & Naughton, 2011;
Lancaster et al., 2020).
• Ensure incoming CEO establishes critical relationships with stakeholders outside the
organization (Bond & Naughton, 2011; Lancaster et al., 2020).
• Incoming CEO establishes critical relationships inside the organization (Bond &
Naughton, 2011; Jones et al., 2008; Lancaster et al., 2020).
• Incoming CEO understands the hospital’s culture (Bond & Naughton, 2011;
Lancaster et al., 2020).
• Incoming CEO aligns with the hospital’s culture (Bond & Naughton, 2011; Lancaster
et al., 2020).
• Incoming CEO develops an understanding of the reality of patient care (Bond &
Naughton, 2011; Lancaster et al., 2020).
• The incoming CEO interviews board members, executive team members,
directorlevel staff members, and local business and community leaders to formulate
a deep understanding of the organization’s culture, market strengths, and
opportunities (Bond & Naughton, 2011; Jones et al., 2009; Lancaster et al., 2020).
• The incoming CEO understands their own preferred job profile, separate from the
presented opportunity (Lancaster et al., 2020).
The new CEO compares their preferred job profile to the presented opportunity
(Lancaster et al., 2020).
The new CEO should research the recruiting agency, the recruiter, and their recent
placements (Lancaster et al., 2020).
• The new CEO should use their network to gain attention from the search committee
(Lancaster et al., 2020).
• The incoming CEO should familiarize themselves with the search committee
members before the search committee interview using their social media and
corporate websites (Lancaster et al., 2020).
• The incoming CEO should prepare, rehearse, and memorize a 5-minute introductory
statement regarding their candidacy (Lancaster et al., 2020).
• The incoming CEO should prepare, rehearse, and memorize answers to possible
interview questions (Lancaster et al., 2020).
67
• The incoming CEO should incorporate information from the board members’ bios
into interview answers where appropriate (Lancaster et al., 2020).
• The incoming CEO should negotiate the employment terms directly with the chair of
the selection committee (Lancaster et al., 2020).
• The incoming CEO should meet with all management and senior leaders within the
first month (Bond & Naughton, 2011; Jones et al., 2009; Lancaster et al., 2020).
• The incoming CEO should meet with all key community members to meet with
during the first year (Bond & Naughton, 2011; Jones et al., 2009; Lancaster et al.,
2020).
The departing chief executive carries out the following activities:
• Outgoing CEO personally informs key board members and organizational staff of
the impending transition (Lancaster et al., 2020).
• The outgoing CEO identifies executive search firms for the board to consider
enlisting to find a new CEO (Lancaster et al., 2020).
• Outgoing CEO provides advice for how administrative team members can best
present themselves to the new CEO (Lancaster et al., 2020).
• Create a list of organizational projects and initiatives to share with the incoming
CEO
• Outgoing CEO demonstrates confidence in and satisfaction with the new CEO to
internal and external stakeholders (Lancaster et al., 2020).
• Through conversations with the incoming CEO, the outgoing CEO explains their
current activities and preparations for the transition (Lancaster et al., 2020).
• Outgoing CEO adopts a consultative rather than directive attitude toward the
incoming CEO (Lancaster et al., 2020).
68
Outgoing CEO adopts a consultative rather than directive attitude toward the
incoming CEO (Lancaster et al., 2020).
• The outgoing CEO is fully out of the organization at the time the incoming CEO starts the
position (Lancaster et al., 2020).
• The outgoing CEO refrains from asking organizational stakeholders how things are going
with the new CEO after the transition (Lancaster et al., 2020).
• The outgoing CEO should be part of the search committee (Lancaster et al., 2020).
• The outgoing CEO should connect the incoming CEO key internal and external stakeholders
(Lancaster et al., 2020).
• The outgoing CEO should review all steps that a transition may require (Lancaster et al.,
2020).
• In cases of voluntary turnover, the outgoing CEO should confirm a personal readiness to
leave (Lancaster et al., 2020).
Related to search firms, the recruiter should help the incoming CEO prepare for the
interview with the search committee (Lancaster et al., 2020), while senior managers carry out
the following activities:
• Senior managers prepare the organization for the new leader (Lancaster et al., 2020).
• Senior managers help employees understand and adapt to the new CEO’s vision (Lancaster
et al., 2020).
• Senior managers adjust organizational structures and processes to fit the new CEO’s vision
(Lancaster et al., 2020).
Chapter 3: Research Methodology
Introduction
This chapter describes the research methodology applied to conduct the study. The
healthcare industry is rapidly growing within the U.S. and around the world due to population
growth, increased life expectancy, and greater incidence of infectious and chronic diseases
(Bureau of Labor Statistics, 2022). However, attrition in the industry, especially at the executive
level, threatens these organizations’ fulfillment of their mission.

69
This chapter begins by restating the research questions that examine the key elements
that are critical in guiding successful executive transitions in large healthcare systems. The
chapter includes a discussion of the research questions, the methodology applied, an
examination of the ethical considerations, describes the research design, and collects
appropriate data (Kumar, 2011; Omi, 2001). Subsequently, relevant data are critically appraised
for validity and reliability.
Restatement of Research Questions
This study identified strategies and organizational practices for chief executive officer
transitions at large hospital systems during times of significant multidimensional change. The
following research questions were examined:
● RQ1: What are the most important organizational practices for CEO transition in
large hospital systems during times of multidimensional change?
● RQ2: Is there a broader framework for CEO transition in large hospital systems
during times of multidimensional change that could be arrived at by further reduction
of the data?
The remainder of this chapter describes the methods that were used in this study. The
next section begins by introducing the research design. Remaining sections describe the
procedures for recruiting and protecting participants, designing the instrument, gathering data,
controlling for my bias as the researcher, and analyzing data.
Research Design
Scholars deploy research projects based on assumptions and perspectives that support
the selection of data collection methods and frame knowledge generation (Hatch & Yanow,
2008). The present study was descriptive and rely upon both qualitative and quantitative
research. Delphi methodology was used to answer the study’s research questions by identifying,
collecting, and analyzing the data related to the most important critical success factors and key

70
elements of CEO transition in large hospital systems during multidimensional organizational
change. This study used the Delphi technique as an instrument to identify, collect, analyze, and
rate data related to the most important organizational practices of a CEO transition in large
hospital systems during times of multidimensional change.
History of the Delphi Method
Delphi nomenclature is derived from an ancient Greek mythology where an oracle
provided estimates or predictions (Sprenkle & Piercy, 2005). The RAND Corporation first
developed the Delphi technique in the 1950s for the purposes of obtaining expert opinions to
inform military strategy (Dalkey & Helmer, 1962; Sprenkle & Piercy, 2005; Winkle et al., 1981).
Skutsch and Hall (1973) advanced the Delphi technique as a methodology to ascertain precise
judgments on complex phenomena where information is unavailable. In the 1970s, the nursing
profession rediscovered the Delphi methodology (Vernon, 2013).
Description and General Application of the Delphi Method
As originally conceived, the Delphi method “involves the repeated individual questioning
of experts (by interview or questionnaire) and avoids direct confrontation of the experts with one
another” (Dalkey & Helmer, 1963, p. 458). The Delphi technique uses this repeated process of
data gathering and analysis for the purpose of reaching agreement among subject matter
experts (Hasson & Keeney, 2011; Keeney et al., 2001a, 2001b). Following each round of data
collection, participants receive a statistical summary of the aggregate results and then are asked
to reconsider their individual responses (Couper, 1984; Goodman, 1987; Whitman,
1990). This process of rating and re-rating the importance of each CEO transition practice is
continued until consensus is reached.
As evidenced by a variety of studies, the Delphi method can be used in quantitative
(Friend, 2001; Garson, 2012), qualitative (Fletcher & Marchildon, 2014; Kincaid, 2003), and
mixed method studies (Brady, 2015; Richards, 2000). Delphi methodology provides researchers

71
with varied degrees of flexibility. For this reason, the approach is considered appropriate for the
present study.
The Delphi method is intended “to obtain the most reliable consensus of opinion of a
group of experts…by a series of intensive questionnaires interspersed with controlled feedback”
(Dalkey & Helmer, 1963, p. 1). Moreover, by underscoring areas of consensus, areas of
disagreement also emerge (Niederberger & Spranger, 2020). Common features across Delphi
studies are protecting experts’ anonymity and administering several survey rounds (Linstone et
al., 2002) through four basic activities: gathering expert opinions (U.S. Department of Health and
Human Services, 1992), aggregating ideas (Cuhls et al., 2015), constructing future predictions
(Kanama et al., 2008; Servan-Schreiber, 2012) and consensus making (McMillan et al., 2016).
Modified Delphi studies incorporate open-ended questions as part of the first-round survey
(Kelly et al., 2017).
Appropriateness of Delphi Method
Delbecq et al. (1975) added that the Delphi approach constitutes “a method for the
systematic solicitation and collection of judgments on a particular topic through a set of carefully
designed sequential questionnaires interspersed with summarized information and feedback of
opinions derived from earlier responses” (p. 10). As such, the Delphi method may be considered
a “constructive effort in building knowledge by all who share in the process” (Kennedy, 2003, p.
505). Given the centrality of the experts’ opinion to this method, selection of an appropriate
number of suitable experts becomes paramount.
A Delphi process is a flexible consensus technique that uses surveys or questionnaires
to collect experts' opinions on a particular phenomenon (Yousuf, 2007). The purpose of the
Delphi technique is to test opinion consensus amongst a group of experts. Delphi's method is an
iterative process that collects and distills the anonymous judgments of experts through a series
of data collection and analysis techniques dispersed with feedback (Skulmoski et al., 2007).

72
When research calls for a technique that is useful in gathering experts’ and practitioners’
judgments, but time, distance and other factors preclude the feasibility of consensus gathering,
the Delphi method application is an instrumental technique (Yousuf, 2007).
Examples of Previous Application of Delphi to the Present Study Topic
Moreover, the Delphi technique has been applied to a number of studies within
healthcare settings (Boulkedid et al., 2011; Keeney et al., 2011; Nasa et al., 2021; Niederberger
& Spranger, 2020). The Delphi method also has been used to identify best practices for
succession planning (Ohnmacht, 2015). The literature review supported the use of the Delphi
methodology to establish consensus on critical elements of a framework for CEO transition in
large hospital systems. The Delphi method is helpful when dealing with problems that “do not
lend themselves to precise analytical techniques but rather could benefit from the subjective
judgments of individuals on a collective basis” (Skulmoski et al., 2007, p. 2). Unlike interview
methods, the Delphi method is particularly helpful for attaining consensus about the study topic
(Wynekoop & Walz, 2000).
Assumptions of the Delphi Method
The assumption underlying this approach is that gaining the perspective of many experts
is better and more valid than gaining the perspective of one expert (Hong & Page, 2004;
Niederberger & Spranger, 2020; Page, 2008). Consequently, Delphi studies often are employed
to reveal areas of consensus, which may increase the likelihood of achieving a significant result
in making decisions (Ab Latif et al., 2016; Hsu & Sandford, 2007; Jorm, 2015; Morgan & Jorm,
2009). By design, the technique allows experts to anonymously exchange opinions without
undue influence from peer pressure (Goodman, 1987). Tersine and Riggs's (1976) characterized
the influences of peers as the “bandwagon effect” (p. 4) created by majority opinion. The Delphi
method can be used when there is incomplete knowledge about a problem or phenomenon
(Adler & Ziglio, 1996).

73
The focus on consensus reveals a fundamental assumption of the Delphi method,
Surowiecki (2004) suggests that all experts’ opinions are equally valid and wise. However,
variations in expertise can affect the achievement of consensus and the trustworthiness of the
results (Thomas & Ganster, 1995).
Strengths and Weaknesses of the Delphi Method
Delphi is a useful technique where the opinions and judgments of practitioners and
experts are necessary (Goodman, 1987; Skulmoski et al., 2007). Delphi methodology is useful
where the opinions and judgments of experts and practitioners are required, but time, distance,
and other extenuating factors make it improbable or impossible for the panel to work conjointly
in the same physical location (Skutsch & Hall, 1973). It is especially applicable when experts are
unable to convene together at the same time. In general, when there is incomplete knowledge
about a phenomenon, the Delphi method works exceptionally well (Skulmoski et al., 2007).
This technique affords the “systematic solicitation and collection of judgments on a
particular topic through a set of carefully designed sequential questionnaires interspersed with
summarized information and feedback of opinions derived from earlier responses” (Delbecq et
al., 1975, p. 10). Using a systematic process of information gathering, the Delphi methodology
assists researchers in gaining consensus regarding future trends and projections through
repeated individual questioning of experts while avoiding direct confrontation between experts
(Dalkey & Helmer, 1962; Yousuf, 2007).
As such, the Delphi approach provides a mechanism for the participants to tackle a
difficult problem (Linstone & Turoff, 1975). This method can be effective and appropriate when
face-to-face meetings of experts would be impractical, infeasible, or subject to peer pressure,
influence, or groupthink that could compromise the results (Goodman, 1987; Linstone & Turoff,
1975; Rasp, 1974; Tersine & Riggs, 1976). In turn, the Delphi method is associated with
enhanced objectivity and credibility due to the use of iterative rounds of data gathering and

74
analysis (Couper, 1984; Reeves & Jauch, 1978; Thomas, 2003; Whitman, 1990). The Delphi
method also is subject to some criticisms and weaknesses. For example, Goodman (1987)
argued that the multiple survey rounds may encourage and promote conformity rather than
genuine agreement. Moreover, there is a lack of clarity about appropriate panel size (Williams &
Webb, 1993) and the measures for gauging consensus (Keeney et al., 2006). In the absence of
clear guidelines, research bias can affect results (Lang, 1994). Guzys et al. (2015) further points
out that criteria are lacking for gauging the quality of the data and results. To control for these
limitations, some researchers advise combining the Delphi method with additional qualitative
research (Jorm, 2015) and meta-analyses (Morgan & Jorm, 2009).
Overall Modified Delphi Methodology Applied in Present Study
In the present study, a qualitative Delphi method was used to answer the research
questions. Various Delphi approaches exist, including traditional Delphi studies that feature an
initial survey with open-ended questions (Jayaratne & Chess, 1984; Whitman, 1990), modified
Delphi studies that use an initial structured survey (Murray & Hammons, 1995), and hybrid
approaches that blend both (Bregar, 2019; Cukor et al., 2013; Quinn et al., 2011). The present
study utilized a modified Delphi approach to make efficient use of participants’ time. Each
element of the study was designed with attention to the analysis unit, population, sample size,
and sample size for the purpose of reaching agreement among experts on the research
questions.
Participant Selection
Delphi studies require researchers to select panel members with expertise relevant to the
study focus, while taking precaution to avoid simply drawing a convenience sample or those
who minimally satisfy the selection criteria (Hill & Fowles, 1975). Delbecq et al. (1975) advised
that panelist “must have a deep interest in the problem and important knowledge or experience

75
to share” (p. 88), while Powell (2003) added, “Experts should be chosen for their work in the
appropriate area and credibility with the target audience” (p. 379).
To solicit recruitment of panelists for this study, a triangulated approach was used. First,
a review of the literature and social media channels identified large hospital systems in the U.S.
that experienced a CEO transition between January 2020 and December 2022. Next, a search
of the organization the CEO transitioned from or to was used to identify the chief human
resources officers and the timeframe of their employment at the institution. In addition. A
keyword search on LinkedIn by the company name identified chief human resources officer
affiliated with the organization.
The triangulated search on LinkedIn, social media and the website of each organization
was utilized to generate the list to recruit panelists. Several aspects of the panel of expert
selection are discussed in this section. Specific topics include the analysis unit, sampling frame,
criteria for inclusion, criteria for exclusion, criteria for maximum variation, and sample size
discussion.
Analysis Unit
The analysis unit was one chief human resources officer with at least one experience
participating in a CEO transition in a U.S.-based large hospital system, defined as a
multihospital, multi-region institution that employs more than 20,000 individuals (American
Hospital Association, 2021). The search on social media affirmed that the individual was
affiliated with the organization at the time of the CEO transition.
Sampling Frame
The population consisted of all chief human resources officers working in large hospital
systems within the United States. The selection process for the present study began with a
search on social media sites that publish turnover of hospital CEOs that was cross referenced
with the American Hospital Association and Association of Academic Medical Center to

76
characterize exits from large hospital systems. A search of the organization website and a
LinkedIn search was used to identify the chief human resources officer of the organization at the
time of the CEOs transition. LinkedIn is a leading repository of professionals globally, making
this an ideal place from which to recruit participants. Individuals who report having a title of chief
human resource officer were identified on LinkedIn. From this list, 50 individuals were invited to
participate in the study. The survey invitation process is discussed later in this chapter. The aim
is to recruit a panel of 30 experts based on inclusion and maximum variation criteria outlined
below, to allow for attrition while achieving a final sample size of 20. The sampling frame also
included chief human resources officers from the researcher’s professional human resources
group, like the Society for Human Resources Management, who meet the criteria for inclusion.
This additional effort was made to expand the range of perspectives reflected in the sampling
frame.
Purposive sampling guided participant recruitment for the present study. Purposive
sampling means that participants are selected due to their ability to provide relevant data or
insights within the parameters of the study (Bernard, 2002; Creswell & Plano Clark, 2011;
Hasson & Keeney, 2011). Participants in the present study had to satisfy criteria for inclusion, as
outlined in a later section. A purposive sample of 50 people was selected from the population
with the aim of retaining a Delphi panel size of 20. Exclusion criteria and criteria for maximum
variation (see sections below) also were applied to yield a suitable sample.
Criteria for Inclusion
Criteria for inclusion as an expert in this study are:
1. Participant has at least 6 months full-time working experience in a large hospital
system.
2. Participant has at least 2 years’ experience as a chief human resources officer.

77
3. Participant has at least one experience participating in a CEO transition in a large
hospital system.
Criteria for Exclusion
Participants were eliminated if they are not available during the proposed study time
frame from February to March 2023 and if they were not able or willing to participate in all three
rounds of surveys during the study time frame.
Criteria for Maximum Variation
If more than 30 individuals volunteer to participate in the study, a sample of 30 was
assembled with a variety of geographic locations and experience levels in large hospital
systems. The criteria for maximum variation are as follows:
1. The selection of final participants first aimed to gather participants reflecting a range
of years of experience in large hospital systems.
2. Panelists were not localized to any particular geographic region beyond working in
the United States.
3. Panelists with the most experience with CEO transition, defined as the number of
transitions they took part in, were sought.
Participants were asked these questions during recruitment (see Appendix B).
Sample Size
Sample sizes for Delphi methods vary greatly but often have a minimum of 10
participants (Akins et al., 2005), although a minimum of eight participants could be adequate
(Hallowel & Gambatese, 2010). Delphi studies in healthcare have ranged from 10 to 1,685
participants (Reid, 1988). To achieve an adequate sample while allowing for attrition (Gargon et
al., 2019; Hall et al., 2018), 50 individuals were invited and, from the volunteers, an initial
sample of 30 was selected. This sample size allowed for transferable but not generalizable
findings. Large samples allow for the surfacing of more data and more diverse opinions at the

78
expense of participation rates, while smaller sample sizes tend to exhibit more participation at
the risk of fewer opinions (Keeney et al., 2001; Linstone & Turoff, 1975; Tersine & Riggs, 1976;
Williams & Webb, 1993).
Protection of Human Subjects
The aim of any Institutional Review Board is to preserve human subjects’ welfare and
dignity. “This process involves submitting a proposal to the board that details the procedures in
the project” (Creswell, 1998, p. 115). The present study satisfied the requirements for exemption
under section 45 CFR 46.101(b)(3) of the federal regulations of the National Institutes of Health.
This section states:
(b) Unless otherwise required by Department or Agency heads, research activities in
which the only involvement of human subjects will be in one or more of the following
categories are exempt from this policy:
Category (2) of the 45 CFR 46.101. Research involving the use of educational tests
(cognitive, diagnostic, aptitude, achievement), survey procedures, interview procedures
or observation of public behavior, unless: (i) information obtained is recorded in such a
manner that human subjects can be identified, directly or through identifiers linked to the
subjects; and (ii) any disclosure of the human subjects’ responses outside the research
could reasonably place the subjects at risk of criminal or civil liability or be damaging to
the subjects’ financial standing, employability, or reputation. (section 45 CFR 46.101)
The researcher filed a claim of exemption with the Pepperdine University Institutional
Review Board in adherence with its policy:
It is the policy of Pepperdine University that all research involving human panel
members must be conducted in accordance with accepted ethical, federal, and
professional standards for research and that all such research must be approved by one
of the University’s Institutional Review Board.
The panelists in this study were volunteers from the adult population who are employed
in a variety of organizations and are not a protected group. No deception was used to get
people to participate in the study, and there is only a small chance that they might tire of the
surveys. Other than receiving a copy of the final dissertation as a reward for their participation
as panelists, no other incentive was offered to study participants. Study findings were presented
only in aggregate, and participants were promised that their responses would remain private.

79
Participants did not face any undue financial or professional risk as a result of the study's data
being disclosed. By participating in this study, participants were not subjected to any civil or
criminal penalties.
Participant confidentiality was protected in several ways in this study. An anonymous
identifier (e.g., Participant 1) was assigned to participants’ responses, and the principal
researcher recorded the participants' responses in a document that was secured with a
password. During the interview process, pseudonyms were given to the shared data that
identified them (such as names, locations, and events). After the study is finished, electronic
versions of the data were stored on a secure server and then permanently deleted after 3 years.
Only the principal researcher, other members of her research team, the Institutional Review
Board, and anyone else required by law had access to the data while it was being stored, and
only for the purpose of collecting, transcribing, or analyzing data. Participants' identities were
kept private. All participants were required to provide their consent to participate before
proceeding to the questionnaire (see Appendix C).
The researcher stored the study data in her home office in a separate file specifically
designated for this study. Any electronic data were archived in a password-protected electronic
file to further protect the data. Three years after the conclusion of the study, the researcher
destroyed all stored data. The remainder of this chapter describes the study procedures.
Instrument Design
In the present modification of the Delphi method, the Round 1 instrument was developed
ahead of time based on the review of literature. The following sections describe several details
of this instrument. The topics reviewed include the initial list of critical items; the use, strengths,
and weaknesses of the Likert scale; the validity and reliability of the instrument; pilot testing of
the instrument; and subsequent round instrument modification.

80
Initial List of Critical Items
The panelists' perceived importance of each item representing practices related to CEO
transition were measured using a 7-point Likert scale survey administered by the researcher
using Qualtrics. Each item was rated in importance from 1 (not at all important) to 7 (critically
important). A survey instrument was distributed in Round 1 and Round 2 to the participants in
this study.
The following questions were posed to participants during recruitment for informational
purposes in anticipation of future analysis of the study data to determine any demographic
patterns and help achieve maximum variation (see Appendix B):
1. How many years have you held a CHRO role?
2. How many years have you worked in a large hospital system?
3. How many CEO transitions have you been involved in?
4. In what state do you work?
Use of Likert Scale
A comprehensive list of practices to support the success of CEO transition was compiled
from the literature review and was placed on the survey instrument. The first round of research
began with sending an email through LinkedIn to each panelist that asks them to rate every item
on the survey. In the first round, panelists also were able to write in any other behaviors or
competencies they consider important. The researcher calculated the median and interquartile
range (IQR) for each item and listed the items in descending order by median (see Appendix D).
Items with IQR ≤ 1 (reflecting 20% of the entire 1-7 possible range) was considered to have
consensus and was removed.
The remaining items were issued as a subsequent survey sent to the panelists for rating.
The researcher again calculated the median and IQR for each item and listed the items in
descending order by median. Items with IQR ≤ 1 were considered to have consensus and were

81
removed. This process iterated for two more rounds, when consensus was achieved.
Consensus was defined as 85% of the survey items indicating consensus (Jayaratne & Chess,
1984; Murray & Hammons, 1995).
Validity and Reliability
Validity and reliability in qualitative studies are reflected in the findings’ credibility.
Credibility is endemic to the Delphi method, as the iterative surveys act as a form of stakeholder
checking (Thomas, 2003). However, this form of credibility relies on high participation rates
(Keeney et al., 2001a, 2001b); therefore, the researcher followed up with panelists who did not
respond to the researcher’s survey invitation within 5 days of its issuance.
Pilot Testing
Before administering the initial survey to participants, the researcher piloted the survey
by sending it to two doctoral candidates known within the researcher’s Ph.D. cohort. These pilot
participants provided feedback on the survey content and ease of use. The survey was adjusted
as needed to promote clarity and participants’ completion.
Subsequent Round Instrument Modification
The researcher sent an email invitation for each survey (see Appendices F and H) to
participants. When each survey closes, responses were downloaded and the median and IQR
were calculated for each item. Items were ranked in descending order by median, and items
indicating consensus (i.e., item IQR ≤ 1) were removed. The remaining items were included in a
subsequent survey. Data collection concluded when 85% of all survey items indicated
consensus.
After each round, the researcher also checked for stability, defined as a change in the
distribution of responses between rounds that is less than 15%. Lincoln and Guba (1985)
suggested that final consensus is achieved if less than 10% of the outstanding items of the
survey show no change or movement in the value of the median, IQR or modal stability after

82
round one to round two calculations result in a difference of zero. The result of the triangulations
confirmed that stability existed, based on the lack of movement in the item.
The study concluded when stability was observed for more than half the original survey
items. Upon completion of the survey rounds, all items were listed from most to least important,
as indicated by median scores. The researcher performed a visual analysis to determine any
themes or categories evident in the data. Visual analysis involved determining whether similarly
ranked items can be grouped into semantically similar categories.
Data Collection
This section outlines the details of data collection for the present study. Data collection in
Delphi studies requires attention to how participants were contacted, how the electronic surveys
were administered, and how follow-up and multi-round communication occurred. The following
sections describe these elements of the present study.
Participant Recruitment
Participant recruitment involved searching on LinkedIn and within the researcher’s
human resources professional group for individuals who meet the inclusion criteria, with the aim
of creating a list of 50 individuals to invite to participate in the study. The researcher then invited
these study candidates to participate via LinkedIn and email following an approved recruitment
script (Appendix E). The invitation explained the study purpose, benefits, eligibility requirements,
and anticipated time commitment. The exclusion criteria and criteria for maximum variation were
applied as described earlier until the researcher achieved a sample of 30 participants. These
individuals were provided with the informed consent information (see Appendix C) when they
click the survey link. They needed to provide their consent to participate before proceeding to
the survey. If this process had yielded less than 30 enrolled panelists, the researcher would
have asked the original 50 to recommend others within their network who might be interested in
participating in the study, in alignment with snowball sampling as described by Patton (1990). If

83
more than 30 individuals had agreed to participate, all volunteers were included in anticipation of
participant attrition by the end of the study while still achieving an ideal representation of Delphi
panel participants.
The researcher reminded the panelists that their identities would remain confidential to
the other participants (unless they independently choose to share their identities) and that the
study consisted of at least three rounds of a Delphi survey to refine a list of organizational
practices and leadership processes that experts deemed to be most important during
multidimensional change that could occur as the result of financial degradation or loss,
economic volatility, brand reputation jeopardy, business calamity, significant loss of talent or
customers. The survey's approximate timeline of 3 to 6 weeks, from February to March 2023,
was reiterated to participants. The researcher made sure that each panelist returned their
signed informed consent form and reminded them to keep a copy for their own records.
Additionally, the researcher checked each panelist's preferred email addresses to ensure that
they would continue to participate in the study. The first round of the Delphi survey was sent to
each panelist at their preferred email address after verification of their intent to participate in the
study, their contact information, and signed consent form.
Follow-up Communication
The researcher sent an email invitation for each survey to participants (see Appendix F),
with the request that they complete the survey within 10 days. A kind email reminder (see
Appendix G) were sent to each panelist again requesting their response within 5 days of the
initial email if the researcher received no response from any panelist within 3 days. The survey
closed on the 11th day.
Multi-Round Communication
For the second and third survey rounds, the researcher sent an email invitation to
participants with the request that they complete the survey within 10 days (see Appendix H). A

84
kind reminder was sent to each panelist who had not provided a response within 5 days. The
survey closed on the 11th day.
Statement of Personal Bias and Lived Experiences
The researcher is a human resource professional who works in a large hospital system.
As a result, researcher bias is inevitable. Researcher bias was reduced in this study through
bracketing and acknowledging her positionality. In turn, bias during panel selection, survey item
selection, analysis, and interpretation of data was anticipated to be reduced. Moreover, the
researcher attempted to allow findings from extant literature to guide the study.
Bracketing and Epoche
The bracketing process, also known as epoche is a method for avoiding bias and
suspending judgment (Gearing, 2004). In the present study, the researcher used memoing
(versus suppression) during data analysis to achieve bracketing. To further enhance objectivity,
each panelist was assigned a unique identifier (e.g., Panelist 1, Panelist 2), and this identifier
was associated with their responses. The coding process further allowed for enhanced
objectivity and reduced researcher bias.
Positionality
Chief executive officers and the board of directors make C-suite appointments with little
attention given to the transition phase and assessing the continuum of leadership practices
required for the newly appointed leaders’ success (Watkins, 2013; Wiggins, 2019). My
association with this study as a researcher is fundamental to the phenomenon of executive
transitions. In my role as chief executive people strategist of a large healthcare system that
employs 25,000 people, my primary objective is to design and lead human capital endeavors
that yield successful business outcomes that increase the likelihood of attaining strategic
imperatives. Strengthening leaders’ capabilities to lead effectively and effectuate people's
engagement at every level to achieve shared goals is a central element of my interest and

85
attention. In addition, an adjacency role I have is as an independent for-profit board of director
member. In this capacity, the board’s emphasis is on selecting and supporting the CEO to lead
the organization with minimal input or exposure to the full spectrum of critical elements that lead
to the executives’ successful transition.
A primary focus of my work is to identify and recommend chief executives, then ensure
leaders are equipped, empowered, and enabled to lead agilely through organizational shifts,
disruptions, and uncertainties. The role serves as the chief architect in designing organizational
practices that increase senior leadership’s effectiveness and to be an influencer who
evangelizes adoption throughout the system. Working with CEO and board of directors, the
collective goal is to design successful chief executive transitions that engage and retain key
individuals when multidimensional factors incite the need for change to sustain business growth.
In leading talent management practices like succession planning, leader assessment, executive
coaching, onboarding, and offboarding, each effort contributes to some aspect of a leader’s
transition. However, independent approaches miss the mark in capturing the essence of the
critical elements that constitute successful transitions and the collective view on replicating
scalable and successful practices. My positionality related to this concern ties to some of my
identities: personal and professional experiences, past and present organizational affiliations,
professional status and position, relationship to anticipated study setting, and anticipated study
population with the phenomenon of transitions.
As Scharp and Thomas (2019) posited, phenomenologists engage in describing what all
participants have in common as they experience a phenomenon should assess how their
positions and experiences might contribute to their interpretations of people's lived experiences
(Creswell & Poth, 2013). Given the extent of my world view of leader transitions and
positionality, a substantial responsibility to offer new knowledge to the literature, it is crucial to

86
acknowledge and disclose who I am concerning this research study by seeking to understand
the part I play in it and the influence I have on it (Cohen et al., 2011).
To accomplish this understanding, a self-examination of my self-consciousness about
participants’ points of view and how this might directly or indirectly influence the findings' design,
execution, and interpretation of the data. Some of my identities contribute to potential blind
spots in addressing this problem. For example, as a chief human resources practitioner, I have
experienced CEO transitions across industries and business sectors with varying degrees of
success and failure, with restrictive positional authority to intervene. Different beliefs and
backgrounds of CEOs and board members may dictate what constitutes success. I may not be
valuing the organizational construct and business norms the CEOs and board members are
used to and the potential biases between them and their colleagues who share in decision
making. I also may not recognize how important it is for chief executives to adapt to and be
successful in a large healthcare system differentiated by industry dynamics and retain their
authenticity. Further, my experience may focus on the individual’s leadership attributes and
characteristics as key contributors to success or failure and focus less on the organizational
constructs of what constitutes a chief executive’s success in transitions, especially during
unprecedented business uncertainties.
I have had experiences of the phenomenon of chief executive transitions in large
organizations, which requires attention to both the design and application of procedures of
epoche and bracketing (Bednall, 2006; Moustakas, 1994). As van Manen (2014) suggests,
research of a phenomenon should be pursued while in a state of wonder in seeking what and
how participants experienced the phenomenon (Moustakas, 1994). Epoche is the suspension of
all judgments without presuppositions until they are founded with more certainty (Creswell &
Poth, 2013; Husserl, 1954/1970). A process of bracketing exists when the researcher brackets
themselves out of the study by discussing their personal experiences with the study not to forget

87
what has been experienced but not to let past knowledge infiltrate while determining
experiences (Creswell, 2016; Giorgi, 2009; van Manen, 2014).
LeVasseur (2003) describes bracketing as suspending understanding in a reflective
manner that cultivates curiosity. To mitigate the impact of my blind spots rooted in positionality, I
integrated epoche sequentially throughout the entire research method from the onset of the
study by setting aside my experiences, as much as possible, to take a fresh perspective toward
examining executive transitions (Lukiv, 2004; Moustakas, 1994; Patton, 1990; Pereira, 2012).
My approach was to decide how and in what way my understanding of executive transitions
would be introduced into the study to ensure respondents’ authentic voices are allowed to
emerge when seeking understanding in data collection and analysis. Conscientiously engaging
with the data at the onset, collection period and how the engagement shifts at the interpretation
stage are the approach to mitigating my positionality biases (Bednall, 2006; Creswell & Poth,
2013; Moerer-Urdahl & Creswell, 2004; Patton, 1990).
Data Analysis
Three rounds of the Delphi survey were administered for the purpose of reaching
consensus. The researcher performed additional analysis on the master list of items to see if a
larger framework could be determined regarding CEO transition in large hospital systems during
times of multidimensional change. The coding procedure for determining the broader framework
in support of RQ2 also is described.
Data Analysis for Research Question Delphi Study
The Delphi approach has been characterized as a committee meeting attended by
anonymous members (Whitman, 1990). The process begins with the researcher requesting
individual input from an expert panel (Keeney et al., 2001b). In traditional Delphi studies, this
first phase invites the experts’ open-ended responses, whereas modified Delphi studies present
the experts with a pre-piloted survey of items to rate based on extant literature (Murray &

88
Hammons, 1995; Uhl, 1983). While traditional approaches allow for the broadest possible
starting point (Whitman, 1990), the large volume of data could overwhelm participants or
significantly increase the risk of researcher bias as they compile the results for inclusion in the
survey (Brooks, 1979; Keeney et al., 2006). After gathering the initial responses, the researcher
reviews and aggregates the data in the form of a subsequent survey of items that panelists are
asked to rate from 1 (not at all important) to 7 (critically very important). The researcher again
aggregates the results into yet another survey with items that panelists are asked to rate. In
each successive survey, only the items that did not indicate consensus were included. The IQR,
calculated as “the absolute value of the difference between the 75th and 25th percentiles
(Rayens & Hahn, 2000, p. 311), were used to determine consensus. Consensus occurred when
the item IQR ≤ 1 (Holden & Wedman, 1993).
Saturation is indicated when consensus is achieved for a sufficient proportion of the
items (85% in the present study [Jayaratne & Chess, 1984; Murray & Hammons, 1995]). In
contrast, stability is achieved when item responses shift by less than 15% from one round to the
next, suggesting that “little, if any, further shifting of positions will occur” (Brooks, 1979, p. 378)
and further insights are unlikely to be reached (Loo, 2002). The present study concluded when
saturation or stability was achieved. Research indicates that this typically occurs within three or
four rounds (Brooks, 1979; Murray & Hammons, 1995; Whitman, 1990). Some researchers
added that a Delphi study should conclude with four rounds even without consensus or stability
to prevent participant fatigue (Dawson & Brucker, 2001; Loo, 2002). In the present study, three
survey rounds were used.
The multiple survey administrations allow panelists to “indicate the extent of their
agreement or disagreement with the opinions that have been expressed, and then re-score their
agreement/disagreement in light of the group responses” (Green & Williams, 1999, p. 199). In

89
this way, participants can revisit and revise their opinions until the study is complete (Hohmann
et al., 2018). The following sections describe each round in more detail.
Round 1. Per the modified Delphi approach, the researcher created the initial survey
(see Appendix I) based on the review of extant literature documented in chapter 2. The objective
of this (and any subsequent) round was to attain “an understanding of how the group views the
issue (i.e., where the members agree or disagree and what they mean by relative terms such as
importance, desirability, or feasibility)” (Linstone & Turoff, 1975, p. 6). Delphi participants are
generally asked to rate each item on a 5- or 7-point Likert scale (Clayton, 1997; Couper, 1984;
Murray & Hammons, 1995). Using the raw data provided by participants, the researcher may
calculate the mean, standard deviation, frequency distribution, median, and interquartile range
(IQR) for each item to reveal variation in participants’ responses (Brooks, 1979; Cyphert & Gant,
1970; Murray & Hammons, 1995; Whitman, 1990). In the present study, a 7-point Likert scale
was used and the median and IQR for each item were calculated.
The IQR and median for each remaining survey item were calculated periodically
between each of the three rounds of data analysis. On a 7-point Likert scale, scholars agree that
items with an IQR of 1 or less are considered to have reached consensus (Ahuja et al.,
2018; De Vet et al., 2005). After eliminating items that reached consensus in Round 1, Rounds 2
and 3 presented the remaining items to the experts for re-rating. The survey was concluded
after reaching stability, defined as change in the distribution of responses between rounds of
less than 15%.
Round 2. The Round 2 survey lists all items that did not attain consensus in Round 1.
Consensus is indicated when the item IQR is ≤ 1. The Round 2 survey presents the Round 1
raw data and median per item (see example in Table 2), which enables participants to view their
individual responses in comparison to the group. Through the subsequent survey questions,
participants are then asked to rate these items again (Brooks, 1979; Tersine & Riggs, 1976).

90
Table 2
Sample Results for Round 2
Rater
Median
Item 1 2 3 4 5 6 7 8 9 10 11 12
13 14 15 Rating a 1 5 2 3 3 2 1
4 5 2 3 5 4 2 5 3 b 1 4 2
2 2 2 1 3 4 2 2 4 3 2 4
2 c 1 5 3 4 4 3 1 5 5 3 4
5 5 3 5 4 d 5 2 4 4 4 4 5
3 2 4 4 2 3 4 2 4
e 2 4 1 1 1 1 2 4 3 1 1 3 2 1 3 2
Note. 1 = not important, 7 = critically important
Round 3 and Subsequent Rounds. The survey for Round 3 (along with the surveys for
any subsequent rounds) presents the previous round’s raw data and median per item and then
asks participants to rate these items again. The present study concluded with Round 3.
Data Analysis for Research Question 2 – Coding
To answer RQ2, the final items selected by the panel were coded. Coding is used during
qualitative research to summarize data into conceptual frameworks (Charmaz, 2006). Coding
allows for data classification (Richards & Morse, 2007), and, ultimately, formulation of a theory
(Corbin & Strauss, 2008). The final list from the previous survey round was subjected to a
modified coding procedure in the present study. The expectation of this altered coding process
is to lead to a larger framework based on the results of the Delphi process. The results of the
coding established the groundwork for subsequent research on the study topic. A second coder
trained in doctoral-level research reviewed the results of the coding to identify possible errors in
the analysis. The researcher and second coder discussed these areas of concern and then
agree upon the final analysis. This process continued until interrater reliability exceeded 85%.
The results of the analysis are reported in chapter 4.

91
Summary
The objective of this chapter was to provide an in-depth look at the research design,
methodology, and methods for carrying out valid and reliable research. The two research
questions for this study were reformulated in this chapter. The chapter also explained the
research design, analysis unit, and population sample size, as well as why the flexible Delphi
technique was used in this study. In addition, the methods for reducing researcher bias and the
criteria for inclusion, exclusion, and maximum variation were defined. Guidelines for protecting
human subjects also were discussed. The survey protocol's peer review validity was also
discussed in the chapter. The methods for data analysis were then presented.
Chapter 4: Data Analysis and Results
The purpose of this study was to identify best practices for CEO transitions at large
hospital systems during times of significant multidimensional change. In this study, a large
hospital system is defined as a multi-hospital, multi-region institution that employs more than
20,000 individuals. Multidimensional change is defined as volatile, complex, uncertain, and
ambiguous conditions that ignite social, economic, and workforce shifts within and outside the
organization. More broadly, the study’s aim was to offer insights to organizations that wish to
improve the success of CEO transitions, especially during times of multidimensional change.
The following research questions were addressed in this study:
1. What are the most important practices for CEO transition in large hospital systems
during times of multidimensional change?
2. Is there a broader framework for CEO transition in large hospital systems during
times of multidimensional change that could be arrived at by further reduction of the
data?
This chapter presents the study findings. A Delphi methodology was used to answer
Research Question 1. Coding was used to answer Research Question 2.

92
Recruitment of Participants
Participants in this study were chief human resources officers who had at least
six months full-time working experience in a large hospital system. The participants had
at least two years’ experience as a chief human resources officer. Also, at least one
experience participating in a CEO transition in a large hospital system.
Based on a search on LinkedIn of chief human resources officers in the United
States and review of the researcher’s professional human resources group, an initial
list of 55 potential study participants was created. The researcher sent each of these
individuals an invitation (see Appendix A) to complete the online Round 1 survey (see
Appendix B). Those who did not complete the survey received a reminder email 5 days
after the initial request. This began the official start of phase one in the Delphi
methodology.
Delphi Phase One
A total of 55 individuals were identified to receive an invitation. Five emails (9%)
bounced. Of the remaining 50 recipients, 30 individuals (60%) completed the survey. Per Turoff
(2002), this sample was sufficient and did not require the application of maximum variation
criteria. All 30 participants completed the survey in its entirety. Table 3 presents the
demographics of the Survey 1 sample. Respondents reflected a range of experience levels.
One third of the sample reported having 5-9.99 years in a CHRO role and 57% reported having
15 or more years of experience in large hospital systems. Participants were well distributed in
terms of their experience levels with CEO transitions. All but one of the respondents were
located in the United States and were geographically distributed (see Figure 15), with the
majority being located in seven states: Georgia (27%), North Carolina (17%), Florida (10%),
Massachusetts, Maryland, Ohio, and Texas (7% each).
93
Phase 1 consisted of a survey (see Appendix B) that included 75 critical items for
successful CEO transition in large hospital systems based on review of extant literature.
Participants were asked to indicate the importance of each item for CEO transition, using the
following scale: 1 = not important at all, 2 = not important, 3 = somewhat not important, 4 = no
opinion, 5 = somewhat important, 6 = important, 7 = critically important. The Phase 1 survey
also included one open-ended item to solicit any additional items considered critical by
participants, and five demographic items. The survey was administered using Qualtrics.
Table 3
Survey 1 Respondent Experience Level
Demographic Category
n
%
Ethnicity
Black
15
50%
White
11
37%
Asian
2
7%
Latinx
1
3%
Two or more races
1
3%
Years in Chief Role
2-2.99 years
5
17%
3-4.99 years
3
10%
5-9.99 years
10
33%
10-14.99 years
5
17%
15 or more years
7
23%
Years in large hospital system
Less than 1 year
4
13%
1-2.99 years
1
3%
3-4.99 years
1
3%
94
5-9.99 years
3
10%
10-14.99 years
4
13%
15 or more years
17
57%
Number of transitions
One
8
27%
Two
8
27%
Three
6
20%
Four
6
20%
Five or more
2
7%
Note. N = 30
Figure 15
Geographic Distribution of Panelists
Note. N = 30; some participants reported having experience working in several states, one
participant cited international experience.
95
The median, IQR, and mode were calculated for each survey item (see Table 4). Items
that had an IQR less than or equal to 1 was deemed to have reached consensus. Of the 75
items, 34 (45%) reached a consensus, leaving 41 (55%) at no consensus. Most items (n = 64,
85.3%) were deemed somewhat to critically important (Median ≥ 5.0) to the success of CEO
transition in large hospital systems.
Table 4
Survey 1 Results
Item
9
The board deliberates and decides on a new successor.
7
0
7
C
19
CHRO serves as an internal advisor to the incoming CEO.
7
0
7
C
22
CHRO assists the new CEO to improve functioning of the senior team.
7
0
7
C
32
The outgoing CEO personally informs key board members and organizational staff of
the impending transition.
7
0
7
C
46
The incoming CEO focuses on getting to know the organization’s people early in the
transition.
7
0
7
C
47
The incoming CEO meets one-on-one with administrative staff and physician leaders
to get to know them.
7
0
7
C
51
The incoming CEO should establish critical relationships inside the organization
7
0
7
C
52
The incoming CEO should seek to understand the hospital’s culture
7
0
7
C
54
The incoming CEO should develop an understanding of the reality of patient care
7
0
7
C
1
The board of directors provides sufficient oversight of the new CEO.
7
1
7
C
2
The board of directors identifies the needed competencies in a new CEO
7
1
7
C
3
Assure the board of directors remains involved as a sounding board and advisor to
the incoming CEO
7
1
7
C
5
The board establishes a CEO search committee.
7
1
7
C
7
The board develops accurate leadership and system profiles for the search.
7
1
7
C
11
The board selects a search firm that understands and respects the organization’s
mission and vision.
7
1
7
C
13
The search committee keeps the board informed and involved throughout the
process of finding possible succession candidates.
7
1
7
C
17
CHRO should identify and address organization culture issues during the transition
7
1
7
C
18
CHRO serves as an internal advisor to the outgoing CEO.
7
1
7
C
24
CHRO acts as an internal advisor to the process
7
1
7
C
25
CHRO supports incoming CEO in learning new perspectives
7
1
7
C
27
CHRO provides support for incoming CEO’s experiences of anxiety, stress, or
alienation
7
1
7
C

96
28
CHRO implements a succession planning framework for executives and mid-level
leaders
7
1
7
C
35
The outgoing CEO creates a list of organizational projects and initiatives to share
with the incoming CEO
7
1
7
C
37
The outgoing CEO, through conversations with the incoming CEO, explains their
current activities and preparations for the transition.
7
1
7
C
38
The outgoing CEO adopts a consultative rather than directive attitude toward the
incoming CEO.
7
1
7
C
39
The outgoing CEO adopts a consultative rather than directive attitude toward the
incoming CEO.
7
1
7
C
48
The incoming CEO holds group meetings with organizational directors.
7
1
7
C
50
The incoming CEO should establish critical relationships with stakeholders outside
the organization
7
1
7
C
Item
55
The incoming CEO interviews board members, executive team members, directorlevel
staff members, and local business and community leaders to formulate a deep
understanding of the organization’s culture, market strengths, and opportunities.
7
1
7
C
66
The incoming CEO should meet with all key community members to meet with during
the first year.
7
1
7
C
67
Administrative team members focus on being open to new and different ways of doing
things
7
1
7
C
73
Senior managers prepare the organization for the new leader.
7
1
7
C
74
Senior managers help employees understand and adapt to the new CEO's vision.
7
1
7
C
75
Senior managers adjust organizational structures and processes to fit the new CEO's
vision.
7
1
7
C
12
The board decides whether internal candidates will be considered as possible
successors and communicates this decision.
7
1.25
7
NC
31
The recruiter should help the incoming CEO prepare for the interview with the search
committee.
7
1.25
7
NC
36
The outgoing CEO demonstrates confidence in and satisfaction with the new CEO to
internal and external stakeholders.
7
1.25
7
NC
68
Each executive team member should create a description of their division, direct
reports, recent accomplishments, and current projects to share with the incoming CEO.
7
1.25
7
NC
69
Administrative staff and outgoing CEO create a list of suggested introductory tasks for
the new CEO to consider during the first 90 days on the job.
6
1.25
6
NC
6
The board finds the executive search firm.
5
2
6
NC
8
The board address the interests of internal candidates.
6
2
6
NC
10
The board selects a search firm that fits the organizational culture.
6
2
7
NC
15
CHRO should create a transition management team to monitor and enhance
organizational health during the change
6
2
7
NC
97
16
CHRO should include patients, community partners, frontline leaders, and diverse
voices from the organization workforce in the transition management team.
5
2
5
NC
21
CHRO facilitates communication between the board and the senior managers.
6
2
7
NC
23
CHRO coordinates the transition process.
7
2
7
NC
26
CHRO supports incoming CEO in adopting new behaviors
7
2
7
NC
29
CHRO creates leadership and system profiles for the new CEO based on the
organization’s culture, market strengths, and opportunities.
6
2
7
NC
34
The outgoing CEO provides advice for how administrative team members can best
present themselves to the new CEO.
4
2
5
NC
41
The outgoing CEO refrains from asking organizational stakeholders how things are
going with the new CEO after the transition.
6
2
7
NC
42
The outgoing CEO should be part of the search committee.
2
2
1
NC
43
The outgoing CEO should connect the incoming CEO key internal and external
stakeholders.
6
2
6
NC
45
The outgoing CEO, in cases of voluntary turnover, confirms a personal readiness to
leave.
5
2
6
NC
49
The incoming CEO should classify the organizational projects and initiatives as (a)
continue, (b) pause, or (c) gather more information.
6
2
6
NC
Item
56
The incoming CEO understands their own preferred job profile, separate from the
presented opportunity.
6
2
6
NC
70
Before the transition, the outgoing CEO spends time with incoming CEO to introduce
them to the local community and key stakeholders.
5
2
4
NC
71
The incoming and outgoing CEO should work together regarding transition timing
and priming the organization for the new CEO's successful entry.
6
2
6
NC
72
The incoming and outgoing CEO should be in regular communication leading up to
the transition.
6
2
6
NC
4
The board allows incoming CEOs more than 3 months and up to 3 years to develop
their vision and have an impact
5
3
7
NC
14
The board should prohibit the incoming CEO from sitting on community boards for at
least two years so they focus on the new role.
2
3
2
NC
20
CHRO manages administrative aspects of the change.
5
3
7
NC
33
The outgoing CEO identifies executive search firms for the board to consider
enlisting to find a new CEO.
3
3
4
NC
40
The outgoing CEO is fully out of the organization at the time the incoming CEO starts
the position.
6
3
6
NC
44
The outgoing CEO should review all steps that a transition may require.
4
3
4
NC
53
The incoming CEO should seek to align with the hospital’s culture
5
3
4
NC
57
The incoming CEO compares their preferred job profile to the presented opportunity.
6
3
6
NC
58
The incoming CEO should research the recruiting agency, the recruiter, and their
recent placements
4
3
3
NC
59
The incoming CEO should use their network to gain attention from the search
committee.
4
3
5
NC
98
60
The incoming CEO should familiarize themselves with the search committee
members before the search committee interview using their social media and
corporate websites.
6
3
7
NC
62
The incoming CEO should prepare, rehearse, and memorize answers to possible
interview questions.
4
3
4
NC
63
The incoming CEO should incorporate information from the board members’ bios into
interview answers where appropriate.
4
3
3
NC
64
The incoming CEO should negotiate the employment terms directly with the chair of
the selection committee.
3
3
2
NC
65
The incoming CEO should meet with all management and senior leaders within the
first month.
6
3
7
NC
30
CHRO conducts a formal review of the new CEO’s performance within their first 6
months on the job.
4
4
7
NC
61
The incoming CEO should prepare, rehearse, and memorize a 5-minute introductory
statement regarding their candidacy.
5
4
7
NC
Note. C = consensus, NC = no consensus
Table 5 presents the items that reached consensus. All 34 items received a ranking of
critically important, on a scale from 1 = not at all important, to 7 = critically important, as
indicated by the median scores reported by the expert panel (N = 30). These 34 items that
reached consensus were excluded from subsequent surveys.
Table 5
Consensus Items from Round 1
Item
9
The board deliberates and decides on a new successor.
7
0
7
19
CHRO serves as an internal advisor to the incoming CEO.
7
0
7
22
CHRO assists the new CEO to improve functioning of the senior team.
7
0
7
32
The outgoing CEO personally informs key board members and organizational staff of the
impending transition.
7
0
7
46
The incoming CEO focuses on getting to know the organization’s people early in the
transition.
7
0
7
47
The incoming CEO meets one-on-one with administrative staff and physician leaders to get to
know them.
7
0
7
51
The incoming CEO should establish critical relationships inside the organization
7
0
7
52
The incoming CEO should seek to understand the hospital’s culture
7
0
7
54
The incoming CEO should develop an understanding of the reality of patient care
7
0
7
1
The board of directors provides sufficient oversight of the new CEO.
7
1
7
2
The board of directors identifies the needed competencies in a new CEO
7
1
7
3
Assure the board of directors remains involved as a sounding board and advisor to the
incoming CEO
7
1
7
99
5
The board establishes a CEO search committee.
7
1
7
7
The board develops accurate leadership and system profiles for the search.
7
1
7
11
The board selects a search firm that understands and respects the organization’s mission and
vision.
7
1
7
13
The search committee keeps the board informed and involved throughout the process of
finding possible succession candidates.
7
1
7
17
CHRO should identify and address organization culture issues during the transition
7
1
7
18
CHRO serves as an internal advisor to the outgoing CEO.
7
1
7
24
CHRO acts as an internal advisor to the process
7
1
7
25
CHRO supports incoming CEO in learning new perspectives
7
1
7
27
CHRO provides support for incoming CEO’s experiences of anxiety, stress, or alienation
7
1
7
28
CHRO implements a succession planning framework for executives and mid-level leaders
7
1
7
35
The outgoing CEO creates a list of organizational projects and initiatives to share with the
incoming CEO
7
1
7
37
The outgoing CEO, through conversations with the incoming CEO, explains their current
activities and preparations for the transition.
7
1
7
38
The outgoing CEO adopts a consultative rather than directive attitude toward the incoming
CEO.
7
1
7
39
The outgoing CEO adopts a consultative rather than directive attitude toward the incoming
CEO.
7
1
7
Item
48
The incoming CEO holds group meetings with organizational directors.
7
1
7
50
The incoming CEO should establish critical relationships with stakeholders outside the
organization
7
1
7
55
The incoming CEO interviews board members, executive team members, director-level
staff members, and local business and community leaders to formulate a deep
understanding of the organization’s culture, market strengths, and opportunities.
7
1
7
66
The incoming CEO should meet with all key community members to meet with during the
first year.
7
1
7
67
Administrative team members focus on being open to new and different ways of doing
things
7
1
7
73
Senior managers prepare the organization for the new leader.
7
1
7
74
Senior managers help employees understand and adapt to the new CEO’s vision.
7
1
7
75
Senior managers adjust organizational structures and processes to fit the new CEO’s
vision.
7
1
7
Note. C = consensus, NC = no consensus
Delphi Phase Two
The 30 Round 1 respondents receive an invitation (see Appendix C) to complete the
Round 2 survey (see Appendix D). Of the remaining 30 recipients, 26 individuals (87%)
completed the survey. This sample was sufficient and did not require the application of
maximum variation criteria (Turoff, 2002). Each respondent completed all survey items.

100
Phase 2 consisted of a survey that included a total of 56 critical items, which
included the 41 items from Round 1 that had not reached consensus plus 15
additional items identified by the expert panel (see Appendix C). The survey was
administered using Qualtrics using an invitation (see Appendix D) and a follow-up
reminder (see Appendix E) to complete the Round 2 survey. Participants were asked
to indicate the importance of each item for CEO transition, using the following scale: 1
= not important at all, 2 = not important, 3 = somewhat not important, 4 = no opinion, 5
= somewhat important, 6 = important, 7 = critically important. Each item also was
presented alongside with its Round 1 median or “(new item)” for items newly identified
by Round 1 respondents.
Similar to Round 1, various statistics were calculated for each item in Round 2,
including the median, IQR, and mode (see Table 6). Items that achieved an IQR of 1 or
less were determined to have reached consensus. Of the 56 items, 35 (37.5%)
reached consensus. The Round 2 results culminated in 69 of the total 90 critical items
(77%) having reached consensus. This was insufficient to reach the intended final
consensus of 85%.

101
Table 6
Round 2 Results
43 The outgoing CEO should connect the incoming CEO key internal and external 6 0 6 C stakeholders.
49 The incoming CEO should classify the organizational projects and initiatives as (a) 6 0 6
C continue, (b) pause, or (c) gather more information.
56 The incoming CEO understands their own preferred job profile, separate from the 6 0 6
C presented opportunity.
57 The incoming CEO compares their preferred job profile to the presented opportunity. 6 0
6 C
81 The incoming CEO should develop deep understanding of any volatile issues within the 7 0.5
7 C system or community which may affect system’s performance and/or reputation.
12 The board decides whether internal candidates will be considered as possible 7 1 7
C successors and communicates this decision.
23 CHRO coordinates the transition process 7 1 7 C
26 CHRO supports incoming CEO in adopting new behaviors 7 1 7 C
36 The outgoing CEO demonstrates confidence in and satisfaction with the new CEO to 7 1
7 C internal and external stakeholders.
65 The incoming CEO should meet with all management and senior leaders within the first 7 1 7 C month.
68 EAT-Each executive team member should create a description of their division, direct 7 1
7 C reports, recent accomplishments, and current projects to share with the incoming CEO.
76 The Board of Directors or the Chairman provides a realistic overview of the current 7 1 7
C state of the company.
82 The incoming CEO has a facilitated integration session with their direct staff within the 7 1
7 C
first 60 days
83 The incoming CEO should not rush organizational change but carefully assess what 7 1
7 C
needs to change/evolve based on input from their CHRO, direct reports, and other key stakeholders
(e.g. physicians, nurses, front line talent).
84 The incoming CEO should strive to enhance diversity through understanding the 7 1 7
C
hospital’s community, challenges around health equity, the hospital’s role in community health
and research, and staff and leadership diversity.
87 MS-Trust and open communication should be developed across all stakeholders 7 1 7 C
involved in the transition, including the Board
89 MS-Ensure there is ample discussion and understanding between board and incoming 7 1
7 C
CEO regarding any significant changes proposed, especially in the first 90 days.
90 MS-The board, executive leadership, and incoming CEO should establish clear 7 1 7
C
business goals and clear understanding of the delegation of authority for the CEO role
4 The board allows incoming CEOs more than 3 months and up to 3 years to develop 6 1 6 C
their vision and have an impact
6 The board finds or endorses the executive search firm. 6 1 6 C
Items

102
10 The board selects a search firm that fits the organizational culture. 6 1 6 C
30 The board conducts formal review of the new CEO’s performance within their first 6 6 1 6
C months on the job.
31 ESC-The search firm or recruiter should help the incoming CEO prepare for the
interview with the search committee.
6 1 7
C 40 The
outgoing CEO is fully
out of the
organization at the
time the incoming
CEO starts the
position.
6 1 6 C
41 The outgoing CEO refrains from asking organizational stakeholders how things are 6 1 7
C going with the new CEO after the transition.
53 The incoming CEO should seek to align with the hospital’s culture 6 1 6 C
69 EAT-Administrative staff and outgoing CEO create a list of suggested introductory 6 1 6
C tasks for the new CEO to consider during the first 90 days on the job.
72 The incoming and outgoing CEO should be in regular communication leading up to the 6 1 6 C transition.
77 CHRO should develop and implement a well-developed communications strategy. 6 1 6 C
86 MS-The overall process and amount of communication between outgoing and incoming 6 1
6 C CEO should be based upon the nature of the departure and business needs.
45 The outgoing CEO, in cases of voluntary turnover, confirms a personal readiness to 5.5 1 5 C leave.
70 MS-Before the transition, the outgoing CEO spends time with the incoming CEO to 5.5 1 5
C introduce them to the local community and key stakeholders.
16 CHRO should include patients, community partners, frontline leaders, and diverse 5 1 5 C
voices from the organization workforce in the transition management team
21 CHRO facilitates communication between the board and the senior managers. 5 1 5
C 42 The outgoing CEO should be part of the search committee. 2 1 2 C
8 The board address the interests of internal candidates. 6 1.5 6 NC
29 CHRO creates leadership and system profiles for the new CEO based on the 6 1.5 6
NC organization’s culture, market strengths, and opportunities.
71 The incoming and outgoing CEO should work together regarding transition timing and 6 1.5
6 NC priming the organization for the new CEO’s successful entry.
88 MS-The incoming CEO should provide transformational and visionary leadership while 6 1.5
6 NC the organization focuses on transactional leadership.
15 CHRO should create a transition management team to monitor and enhance 6 2 6 NC
organizational health during the change
60 The incoming CEO should familiarize themselves with the search committee members 6 2
6 NC before the search committee interview using their social media and corporate websites.
79 ESC-An external executive coach should assist the incoming CEO with transition and 6 2
7 NC integration matters.
20 CHRO manages administrative aspects of the change. 5.5 2 6 NC
61 The incoming CEO should prepare, rehearse, and memorize a 5-minute introductory 5 2
5 NC statement regarding their candidacy.
Items
103
78 ESC-A CEO boot camp should be arranged for the incoming CEO. 5 2 5 NC
85 The incoming CEO should ensure that many aspects of the organization remain in 5 2 5
NC place for continuity and stability.
34 The outgoing CEO provides advice for how administrative team members can best 4 2 5
NC present themselves to the new CEO.
58 The incoming CEO should research the recruiting agency, the recruiter, and their 4 2 4
NC recent placements
59 The incoming CEO should use their network to gain attention from the search
committee.
4 2 4 NC
Items
63
The incoming CEO should incorporate information from the board members’ bios into
interview answers where appropriate.
4
2
5
NC
80
ESC-An external CEO succession expert who is experienced, has no internal bias, and
has benchmarks on other successful CEO transitions should lead the transition.
4
2
4
NC
33
The outgoing CEO identifies executive search firms for the board to consider enlisting
to find a new CEO.
3
2
2
NC
14
The board should prohibit the incoming CEO from sitting on community boards for at
least two years so they focus on the new role.
2
2
2
NC
62
The incoming CEO should prepare, rehearse, and memorize answers to possible
interview questions.
4
2.5
5
NC
44
The outgoing CEO should review all steps that a transition may require.
5
3
3
NC
64
The incoming CEO should negotiate the employment terms directly with the chair of the
selection committee.
3
3
2
NC
Note. C = consensus, NC = no consensus
Table 7 summarizes the items that reached consensus, sorted by level of importance, as
determined by the panel of experts (n = 26). Importance was indicated by median score,
reported on a scale from 1 (not at all important) to 7 (critically important). These 35 items that
attained consensus were excluded from the Round 3 survey.
Table 7
Consensus Items from Round 2
Items
104
81
The incoming CEO should develop deep understanding of any volatile issues within the
system or community which may affect system’s performance and/or reputation.
7
0.5
7
12
The board decides whether internal candidates will be considered as possible successors
and communicates this decision.
7
1
7
23
CHRO coordinates the transition process
7
1
7
26
CHRO supports incoming CEO in adopting new behaviors
7
1
7
36
The outgoing CEO demonstrates confidence in and satisfaction with the new CEO to
internal and external stakeholders.
7
1
7
65
The incoming CEO should meet with all management and senior leaders within the first
month.
7
1
7
68
EAT-Each executive team member should create a description of their division, direct
reports, recent accomplishments, and current projects to share with the incoming CEO.
7
1
7
76
The Board of Directors or the Chairman provides a realistic overview of the current state of
the company.
7
1
7
82
The incoming CEO has a facilitated integration session with their direct staff within the first
60 days
7
1
7
Items
83
The incoming CEO should not rush organizational change but carefully assess what needs
to change/evolve based on input from their CHRO, direct reports, and other key
stakeholders (e.g. physicians, nurses, front line talent).
7
1
7
84
The incoming CEO should strive to enhance diversity through understanding the hospital’s
community, challenges around health equity, the hospital’s role in community health and
research, and staff and leadership diversity.
7
1
7
87
MS-Trust and open communication should be developed across all stakeholders involved in
the transition, including the Board
7
1
7
89
MS-Ensure there is ample discussion and understanding between board and incoming
CEO regarding any significant changes proposed, especially in the first 90 days.
7
1
7
90
MS-The board, executive leadership, and incoming CEO should establish clear business
goals and clear understanding of the delegation of authority for the CEO role
7
1
7
43
The outgoing CEO should connect the incoming CEO key internal and external
stakeholders.
6
0
6
49
The incoming CEO should classify the organizational projects and initiatives as (a)
continue, (b) pause, or (c) gather more information.
6
0
6
56
The incoming CEO understands their own preferred job profile, separate from the
presented opportunity.
6
0
6
57
The incoming CEO compares their preferred job profile to the presented opportunity.
6
0
6
4
The board allows incoming CEOs more than 3 months and up to 3 years to develop their
vision and have an impact
6
1
6
6
The board finds or endorses the executive search firm.
6
1
6
10
The board selects a search firm that fits the organizational culture.
6
1
6
30
The board conducts formal review of the new CEO’s performance within their first 6 months
on the job.
6
1
6
31
ESC-The search firm or recruiter should help the incoming CEO prepare for the interview
with the search committee.
6
1
7

105
40
The outgoing CEO is fully out of the organization at the time the incoming CEO starts the
position.
6
1
6
41
The outgoing CEO refrains from asking organizational stakeholders how things are going
with the new CEO after the transition.
6
1
7
53
The incoming CEO should seek to align with the hospital’s culture
6
1
6
69
EAT-Administrative staff and outgoing CEO create a list of suggested introductory tasks for
the new CEO to consider during the first 90 days on the job.
6
1
6
72
The incoming and outgoing CEO should be in regular communication leading up to the
transition.
6
1
6
77
CHRO should develop and implement a well-developed communications strategy.
6
1
6
86
MS-The overall process and amount of communication between outgoing and incoming
CEO should be based upon the nature of the departure and business needs.
6
1
6
45
The outgoing CEO, in cases of voluntary turnover, confirms a personal readiness to leave.
5.5
1
5
70
MS-Before the transition, the outgoing CEO spends time with the incoming CEO to
introduce them to the local community and key stakeholders.
5.5
1
5
16
CHRO should include patients, community partners, frontline leaders, and diverse voices
from the organization workforce in the transition management team
5
1
5
21
CHRO facilitates communication between the board and the senior managers.
5
1
5
42
The outgoing CEO should be part of the search committee.
2
1
2
After Round 2, 77% of items had reached consensus based on the IQR score. Because
this was not sufficient to satisfy the threshold for final consensus (i.e., 85% of items reaching
consensus), it was necessary to conduct a stability analysis. A stability analysis compares the
differences in median, mode, and IQR score on non-consensus items from Round 1 to Round 2.
The results of the stability analysis are displayed in Table 8.
As of Round 2, there remained 21 unstable items. Of these, 14 displayed no change in
median from Round 1 to Round 2. Four items showed no IQR difference across the two rounds,
and five items displayed no change in mode. The Median Stability Index (MeCI), the percentage
of remaining items for which the median changed from Round 1 to Round 2, was 6%. The IQR
Stability Index (IQRCI), the percentage of remaining items for which the Interquartile Range
changed from Round 1 to Round 2, was 4%. The Modal Stability Index (MoCI), the percentage of
remaining items for which the mode changed from Round 1 to Round 2, was 16%. One of the
three indexes did not fall below the 10% threshold for stability, confirming that the study had not
yet reached final stability or consensus, requiring a third round of Delphi analysis.

106
Table 8
Round 2 Stability Analysis
Differences R1–R2
Item
8
The board address the interests of internal candidates.
0.00
0.50
0.00
14
The board should prohibit the incoming CEO from sitting on community boards for at
least two years so they focus on the new role.
0.00
1.00
0.00
15
CHRO should create a transition management team to monitor and enhance
organizational health during the change
0.00
0.00
1.00
20
CHRO manages administrative aspects of the change.
0.50
1.00
1.00
29
CHRO creates leadership and system profiles for the new CEO based on the
organization’s culture, market strengths, and opportunities.
0.00
0.50
1.00
33
The outgoing CEO identifies executive search firms for the board to consider
enlisting to find a new CEO.
0.00
1.00
2.00
34
The outgoing CEO provides advice for how administrative team members can best
present themselves to the new CEO.
0.00
0.00
0.00
44
The outgoing CEO should review all steps that a transition may require.
1.00
0.00
1.00
58
The incoming CEO should research the recruiting agency, the recruiter, and their
recent placements
0.00
1.00
1.00
59
The incoming CEO should use their network to gain attention from the search
committee.
0.00
1.00
1.00
60
The incoming CEO should familiarize themselves with the search committee
members before the search committee interview using their social media and
corporate websites.
0.00
1.00
1.00
61
The incoming CEO should prepare, rehearse, and memorize a 5-minute introductory
statement regarding their candidacy.
0.00
2.00
2.00
62
The incoming CEO should prepare, rehearse, and memorize answers to possible
interview questions.
0.00
0.50
1.00
63
The incoming CEO should incorporate information from the board members’ bios into
interview answers where appropriate.
0.00
1.00
2.00
64
The incoming CEO should negotiate the employment terms directly with the chair of the
selection committee.
0.00
0.00
0.00
71
The incoming and outgoing CEO should work together regarding transition timing
and priming the organization for the new CEO’s successful entry.
0.00
0.50
0.00
107
Delphi Phase Three
The 30 initial respondents received an invitation (see Appendix E) to complete the Round
3 survey (see Appendix F). Of the 30 recipients, 24 individuals (80%) completed the survey. This
sample was sufficient and did not require the application of maximum variation criteria (Turoff,
2002). Each respondent completed all survey items.
Phase 3 consisted of a survey that included a total of 21 critical items that had
not reached consensus through the previous rounds (see Appendix G). The survey was
administered using Qualtrics using an invitation (see Appendix H) and a follow-up
reminder (see Appendix I) to complete the Round 3 survey. Participants were asked to
indicate the importance of each item for CEO transition, using the following scale: 1 =
not important at all, 2 = not important, 3 = somewhat not important, 4 = no opinion, 5 =
somewhat important, 6 = important, 7 = critically important. Each item also was
presented alongside with its Round 2 median as identified by Round 2 respondents.
Table 9
Round 3 Results
8 The board address the interests of internal candidates. 6 0 6 C
CHRO should create a transition management team to monitor and enhance
15 organizational health during the change 6 0 6 C
20 CHRO manages administrative aspects of the change. 6 1 6 C
CHRO creates leadership and system profiles for the new CEO based on the
29 organization’s culture, market strengths, and opportunities. 6 0 6 C
The outgoing CEO identifies executive search firms for the board to consider enlisting
33 to find a new CEO. 2 1 2 C
44 The outgoing CEO should review all steps that a transition may require. 5 0 5 C
The incoming CEO should research the recruiting agency, the recruiter, and their
58 recent placements 4 1 4 C
The incoming CEO should use their network to gain attention from the search
59 committee. 3 1 3 C
The incoming CEO should familiarize themselves with the search committee members
60 before the search committee interview using their social media and corporate websites. 6 1 6
C The incoming and outgoing CEO should work together regarding transition timing and
71 priming the organization for the new CEO’s successful entry. 6 1 6 C
78 ESC-A CEO boot camp should be arranged for the incoming CEO. 5 1 5 C
Item
108
ESC-An external executive coach should assist the incoming CEO with transition and
79 integration matters. 6 1 6 C
The incoming CEO should ensure that many aspects of the organization remain in
85 place for continuity and stability. 5 0 5 C
MS-The incoming CEO should provide transformational and visionary leadership while
88 the organization focuses on transactional leadership. 6 1 6 C
The board should prohibit the incoming CEO from sitting on community boards for at
14 least two years so they focus on the new role. 2.5 2 2 NC
The outgoing CEO provides advice for how administrative team members can best
34 present themselves to the new CEO. 4 2 4 NC
The incoming CEO should prepare, rehearse, and memorize a 5-minute introductory
61 statement regarding their candidacy. 5 2 5 NC
The incoming CEO should prepare, rehearse, and memorize answers to possible
62 interview questions. 4 2 4 NC
The incoming CEO should incorporate information from the board members’ bios into
63 interview answers where appropriate. 4 2 4 NC
The incoming CEO should negotiate the employment terms directly with the chair of the
64 selection committee. 3 2 3 NC
ESC-An external CEO succession expert who is experienced, has no internal bias, and
80 has benchmarks on other successful CEO transitions should lead the transition. 4 2 4 NC
Note. C = consensus, NC = no consensus
Similar to Rounds 1 and 2, various statistics were calculated for each item in
Round 3, including the median, IQR, and mode (see Table 9). Items that achieved an
IQR of 1 or less were determined to have reached consensus. Of the 21 items, 14
(67%) reached consensus. The Round 3 results culminated in 83 of the total 90 critical
items (92.2%) having reached consensus, which exceeded the final needed
consensus (85%).
Table 10
Round 3 Items with Consensus
8 The board address the interests of internal candidates. 6 0 6
CHRO should create a transition management team to monitor and enhance
15 organizational health during the change 6 0 6
20 CHRO manages administrative aspects of the change. 6 1 6
CHRO creates leadership and system profiles for the new CEO based on the
29 organization’s culture, market strengths, and opportunities. 6 0 6
The outgoing CEO identifies executive search firms for the board to consider enlisting
33 to find a new CEO. 2 1 2
Item
Item
109
44 The outgoing CEO should review all steps that a transition may require. 5 0 5
The incoming CEO should research the recruiting agency, the recruiter, and their
58 recent placements 4 1 4
The incoming CEO should use their network to gain attention from the search
59 committee. 3 1 3
The incoming CEO should familiarize themselves with the search committee members
60 before the search committee interview using their social media and corporate websites. 6 1 6
The incoming and outgoing CEO should work together regarding transition timing and
71 priming the organization for the new CEO’s successful entry. 6 1 6
78 ESC-A CEO boot camp should be arranged for the incoming CEO. 5 1 5
ESC-An external executive coach should assist the incoming CEO with transition and
79 integration matters. 6 1 6
85
The incoming CEO should ensure that many aspects of the organization remain in place
for continuity and stability.
5
0
5
88
MS-The incoming CEO should provide transformational and visionary leadership while
the organization focuses on transactional leadership.
6
1
6
After the completion of Round 3, 83 (92.2%) of items had reached consensus based on
the IQR score. Final consensus is automatically reached when 85% or more items have reached
individual consensus. Additionally, stability analysis was conducted on the items that did not
achieve consensus in Round 3. The stability analysis compared the differences in median, mode,
and IQR score on the non-consensus items from Round 2 to Round 3. These results are
presented in Table 11.
Table 11
Round 3 Stability Analysis
Differences R1–R2
Item
14
The board should prohibit the incoming CEO from sitting on community boards for at
least two years so they focus on the new role.
0.50
0.00
0.00
34
The outgoing CEO provides advice for how administrative team members can best
present themselves to the new CEO.
0.00
0.00
1.00
61
The incoming CEO should prepare, rehearse, and memorize a 5-minute introductory
statement regarding their candidacy.
0.00
0.00
0.00
62
The incoming CEO should prepare, rehearse, and memorize answers to possible
interview questions.
0.00
0.50
1.00
Item
110
63
The incoming CEO should incorporate information from the board members’ bios into
interview answers where appropriate.
0.00
0.00
1.00
64
The incoming CEO should negotiate the employment terms directly with the chair of the
selection committee.
0.00
1.00
1.00
80
ESC-An external CEO succession expert who is experienced, has no internal bias, and
has benchmarks on other successful CEO transitions should lead the transition.
0.00
0.00
0.00
As of Round 3, there remained seven unstable items. Of these, six displayed no change
in median from Round 2 to Round 3. Five items showed no IQR difference across the two
rounds, and three items displayed no change in mode. The Median Stability Index (MeCI), the
percentage of remaining items for which the median changed from Round 2 to Round 3, was
30%. The IQR Stability Index (IQRCI), the percentage of remaining items for which the
Interquartile Range changed from Round 2 to Round 3, was 20%. The Modal Stability Index
(MoCI), the percentage of remaining items for which the mode changed from Round 2 to Round
3, was 33%. Although these indexes did not fall below the 10% threshold for stability, the study
had reached final stability or consensus, given that 92.2.% of items were stable.
Final Consensus
Upon conclusion of all three surveys, 83 of the 90 critical items (92.2%) reached
consensus. Table 12 shows all items that had reached consensus, sorted by level of importance
(highest to lowest median score) and the corresponding Likert-scale ranking.
Table 12
All Items with Consensus
Item
Rating
9
The board deliberates and decides on a new successor.
7
0
Critically
Important
19
CHRO serves as an internal advisor to the incoming CEO.
7
0
Critically
Important
22
CHRO assists the new CEO to improve functioning of the senior team.
7
0
Critically
Important
32
The outgoing CEO personally informs key board members and organizational staff
of the impending transition.
7
0
Critically
Important
111
46
The incoming CEO focuses on getting to know the organization’s people early in
the transition.
7
0
Critically
Important
47
The incoming CEO meets one-on-one with administrative staff and physician
leaders to get to know them.
7
0
Critically
Important
51
The incoming CEO should establish critical relationships inside the organization
7
0
Critically
Important
52
The incoming CEO should seek to understand the hospital’s culture
7
0
Critically
Important
54
The incoming CEO should develop an understanding of the reality of patient
care
7
0
Critically
Important
1
The board of directors provides sufficient oversight of the new CEO.
7
1
Critically
Important
2
The board of directors identifies the needed competencies in a new CEO
7
1
Critically
Important
3
Assure the board of directors remains involved as a sounding board and advisor to
the incoming CEO
7
1
Critically
Important
5
The board establishes a CEO search committee.
7
1
Critically
Important
Item
Rating
7
The board develops accurate leadership and system profiles for the search.
7
1
Critically
Important
11
The board selects a search firm that understands and respects the organization’s
mission and vision.
7
1
Critically
Important
13
The search committee keeps the board informed and involved throughout the
process of finding possible succession candidates.
7
1
Critically
Important
17
CHRO should identify and address organization culture issues during the
transition
7
1
Critically
Important
18
CHRO serves as an internal advisor to the outgoing CEO.
7
1
Critically
Important
24
CHRO acts as an internal advisor to the process
7
1
Critically
Important
25
CHRO supports incoming CEO in learning new perspectives
7
1
Critically
Important
27
CHRO provides support for incoming CEO’s experiences of anxiety, stress, or
alienation
7
1
Critically
Important
28
CHRO implements a succession planning framework for executives and midlevel
leaders
7
1
Critically
Important
35
The outgoing CEO creates a list of organizational projects and initiatives to
share with the incoming CEO
7
1
Critically
Important
37
The outgoing CEO, through conversations with the incoming CEO, explains their
current activities and preparations for the transition.
7
1
Critically
Important
38
The outgoing CEO adopts a consultative rather than directive attitude toward the
incoming CEO.
7
1
Critically
Important
39
The outgoing CEO adopts a consultative rather than directive attitude toward the
incoming CEO.
7
1
Critically
Important
48
The incoming CEO holds group meetings with organizational directors.
7
1
Critically
Important
112
50
The incoming CEO should establish critical relationships with stakeholders
outside the organization
7
1
Critically
Important
55
The incoming CEO interviews board members, executive team members, director-
level staff members, and local business and community leaders to formulate a
deep understanding of the organization’s culture, market strengths, and
opportunities.
7
1
Critically
Important
66
The incoming CEO should meet with all key community members to meet with
during the first year.
7
1
Critically
Important
67
Administrative team members focus on being open to new and different ways of
doing things
7
1
Critically
Important
73
Senior managers prepare the organization for the new leader.
7
1
Critically
Important
74
Senior managers help employees understand and adapt to the new CEO's vision.
7
1
Critically
Important
75
Senior managers adjust organizational structures and processes to fit the new
CEO's vision.
7
1
Critically
Important
81
The incoming CEO should develop deep understanding of any volatile issues
within the system or community which may affect system’s performance and/or
reputation.
7
0.5
Critically
Important
12
The board decides whether internal candidates will be considered as possible
successors and communicates this decision.
7
1
Critically
Important
23
CHRO coordinates the transition process
7
1
Critically
Important
Item
Rating
26
CHRO supports incoming CEO in adopting new behaviors
7
1
Critically
Important
36
The outgoing CEO demonstrates confidence in and satisfaction with the new CEO
to internal and external stakeholders.
7
1
Critically
Important
65
The incoming CEO should meet with all management and senior leaders within the
first month.
7
1
Critically
Important
68
EAT-Each executive team member should create a description of their division,
direct reports, recent accomplishments, and current projects to share with the
incoming CEO.
7
1
Critically
Important
76
The Board of Directors or the Chairman provides a realistic overview of the current
state of the company.
7
1
Critically
Important
82
The incoming CEO has a facilitated integration session with their direct staff within
the first 60 days
7
1
Critically
Important
83
The incoming CEO should not rush organizational change but carefully assess
what needs to change/evolve based on input from their CHRO, direct reports, and
other key stakeholders (e.g. physicians, nurses, front line talent).
7
1
Critically
Important
84
The incoming CEO should strive to enhance diversity through understanding the
hospital’s community, challenges around health equity, the hospital’s role in
community health and research, and staff and leadership diversity.
7
1
Critically
Important
87
MS-Trust and open communication should be developed across all stakeholders
involved in the transition, including the Board
7
1
Critically
Important
89
MS-Ensure there is ample discussion and understanding between board and
incoming CEO regarding any significant changes proposed, especially in the first
90 days.
7
1
Critically
Important
113
90
MS-The board, executive leadership, and incoming CEO should establish clear
business goals and clear understanding of the delegation of authority for the CEO
role
7
1
Critically
Important
43
The outgoing CEO should connect the incoming CEO key internal and external
stakeholders.
6
0
Important
49
The incoming CEO should classify the organizational projects and initiatives as (a)
continue, (b) pause, or (c) gather more information.
6
0
Important
56
The incoming CEO understands their own preferred job profile, separate from the
presented opportunity.
6
0
Important
57
The incoming CEO compares their preferred job profile to the presented
opportunity.
6
0
Important
4
The board allows incoming CEOs more than 3 months and up to 3 years to
develop their vision and have an impact
6
1
Important
6
The board finds or endorses the executive search firm.
6
1
Important
10
The board selects a search firm that fits the organizational culture.
6
1
Important
30
The board conducts formal review of the new CEO’s performance within their first
6 months on the job.
6
1
Important
31
ESC-The search firm or recruiter should help the incoming CEO prepare for the
interview with the search committee.
6
1
Important
40
The outgoing CEO is fully out of the organization at the time the incoming CEO
starts the position.
6
1
Important
41
The outgoing CEO refrains from asking organizational stakeholders how things are
going with the new CEO after the transition.
6
1
Important
53
The incoming CEO should seek to align with the hospital’s culture
6
1
Important
Item
Rating
69
EAT-Administrative staff and outgoing CEO create a list of suggested introductory
tasks for the new CEO to consider during the first 90 days on the job.
6
1
Important
72
The incoming and outgoing CEO should be in regular communication leading up to
the transition.
6
1
Important
77
CHRO should develop and implement a well-developed communications strategy.
6
1
Important
86
MS-The overall process and amount of communication between outgoing and
incoming CEO should be based upon the nature of the departure and business
needs.
6
1
Important
8
The board address the interests of internal candidates.
6
0
Important
15
CHRO should create a transition management team to monitor and enhance
organizational health during the change
6
0
Important
20
CHRO manages administrative aspects of the change.
6
1
Important
29
CHRO creates leadership and system profiles for the new CEO based on the
organization’s culture, market strengths, and opportunities.
6
0
Important
60
The incoming CEO should familiarize themselves with the search committee
members before the search committee interview using their social media and
corporate websites.
6
1
Important
71
The incoming and outgoing CEO should work together regarding transition timing
and priming the organization for the new CEO’s successful entry.
6
1
Important

114
79
ESC-An external executive coach should assist the incoming CEO with transition
and integration matters.
6
1
Important
88
MS-The incoming CEO should provide transformational and visionary leadership
while the organization focuses on transactional leadership.
6
1
Important
45
The outgoing CEO, in cases of voluntary turnover, confirms a personal readiness
to leave.
5.
5
1
Important
70
MS-Before the transition, the outgoing CEO spends time with the incoming CEO to
introduce them to the local community and key stakeholders.
5.
5
1
Important
16
CHRO should include patients, community partners, frontline leaders, and diverse
voices from the organization workforce in the transition management team
5
1
Somewhat
Important
21
CHRO facilitates communication between the board and the senior managers.
5
1
Somewhat
Important
44
The outgoing CEO should review all steps that a transition may require.
5
0
Somewhat
Important
78
ESC-A CEO boot camp should be arranged for the incoming CEO.
5
1
Somewhat
Important
85
The incoming CEO should ensure that many aspects of the organization remain in
place for continuity and stability.
5
0
Somewhat
Important
58
The incoming CEO should research the recruiting agency, the recruiter, and their
recent placements
4
1
No Opinion
59
The incoming CEO should use their network to gain attention from the search
committee.
3
1
Somewhat
Not
Important
42
The outgoing CEO should be part of the search committee.
2
1
Not
Important
33
The outgoing CEO identifies executive search firms for the board to consider
enlisting to find a new CEO.
2
1
Not
Important
Coding
Research Question 2 examined whether a broader framework existed for CEO transition
in large hospital systems during times of multidimensional change. Answering this research
question required further reduction of the data using content analysis. This process involved
examining the items receiving consensus using thematic analysis. The 83 items were organized
into seven themes:
Theme 1: CHRO: Roles the CHRO should fulfill and activities they should carry out.
These include acting as a process consultant and communication/integration champion for the
transition, coaching and counseling the incoming CEO, supporting organizational performance
through the transition, leading the organization through the transition to optimize organizational
health and performance.

115
Theme 2: Board of Directors: Activities the board needs to enact, including leading and
outlining the parameters for search process, selecting the new CEO, orienting and overseeing
the new CEO, and evaluating new CEO in an appropriate time frame.
Theme 3: Outgoing CEO: Activities the outgoing CEO should carry out, including
communicating the organization about the transition, demonstrating confidence in new CEO,
collaborating and communicating with the incoming CEO to promote a smooth transition, exiting
completely and expediently, and adapting their involvement in the transition based on the nature
of the exit.
Theme 4: Incoming CEO: Activities the new CEO should carry out, including assuring
they understand and want the position, assessing and aligning with the organization and
community, building relationships with all stakeholders, formulating a plan, collaborating and
communicating with the outgoing CEO to promote smooth transition. Panelists expressed,
however, that activities related to the new CEO securing a job offer were not relevant to the
success of the transition.
Theme 5: Organizational leaders: Activities that executives, senior leaders, and managers
should carry out, including supporting employees in following the new CEO’s vision and adjust
the organization as needed.
Theme 6: Multiple stakeholders: The board, new CEO, senior leadership, and executives
should develop mutual trust and build common understanding about the organization’s current
and future state through ample communication. Organization members should collaborate to
promote fulfillment of new CEO’s vision.
Theme 7: External supports: Coaches and succession experts should communicate
extensively with board and equip the incoming CEO to get the job and navigate the transition
well.

116
These codes were shared with and validated by two doctoral-level qualitative
researchers. These peer reviewers were asked to review the coding results and determine
whether they agreed with the analysis, based upon the 83 items that had attained consensus.
Both peer reviewers agreed with the analysis. Table 13 presents the coding for each critical item.
Table 13
Coding Results for Items Reaching Consensus
Item
Code
Administrative team members focus on being open to new and different ways of doing things
Multiple
Stakeholders
Assure the board of directors remains involved as a sounding board and advisor to the incoming
CEO
CHRO
CHRO acts as an internal advisor to the process
CHRO
CHRO assists the new CEO to improve functioning of the senior team.
CHRO
CHRO coordinates the transition process
CHRO
CHRO creates leadership and system profiles for the new CEO based on the organization’s
culture, market strengths, and opportunities.
CHRO
CHRO facilitates communication between the board and the senior managers.
CHRO
CHRO implements a succession planning framework for executives and mid-level leaders
CHRO
CHRO manages administrative aspects of the change.
CHRO
CHRO provides support for incoming CEO’s experiences of anxiety, stress, or alienation
CHRO
CHRO serves as an internal advisor to the incoming CEO.
CHRO
CHRO serves as an internal advisor to the outgoing CEO.
CHRO
Item
Code
CHRO should create a transition management team to monitor and enhance organizational
health during the change
CHRO
CHRO should develop and implement a well-developed communications strategy.
CHRO
CHRO should identify and address organization culture issues during the transition
CHRO
CHRO should include patients, community partners, frontline leaders, and diverse voices from
the organization workforce in the transition management team
CHRO
CHRO supports incoming CEO in adopting new behaviors
CHRO
CHRO supports incoming CEO in learning new perspectives
CHRO
Administrative staff and outgoing CEO create a list of suggested introductory tasks for the new
CEO to consider during the first 90 days on the job.
Multiple
Stakeholders
Each executive team member should create a description of their division, direct reports, recent
accomplishments, and current projects to share with the incoming CEO.
Multiple
Stakeholders
A CEO boot camp should be arranged for the incoming CEO.
External
supports
An external executive coach should assist the incoming CEO with transition and integration
matters.
External
supports
The search firm or recruiter should help the incoming CEO prepare for the interview with the
search committee.
External
supports

117
Before the transition, the outgoing CEO spends time with the incoming CEO to introduce them to
the local community and key stakeholders.
Outgoing CEO
Ensure there is ample discussion and understanding between board and incoming CEO
regarding any significant changes proposed, especially in the first 90 days.
Multiple
Stakeholders
The board, executive leadership, and incoming CEO should establish clear business goals and
clear understanding of the delegation of authority for the CEO role
Multiple
Stakeholders
The incoming CEO should provide transformational and visionary leadership while the
organization focuses on transactional leadership.
Multiple
Stakeholders
The overall process and amount of communication between outgoing and incoming CEO should
be based upon the nature of the departure and business needs.
Outgoing CEO
Trust and open communication should be developed across all stakeholders involved in the
transition, including the Board
Multiple
Stakeholders
Senior managers adjust organizational structures and processes to fit the new CEO's vision.
Organizational
leaders
Senior managers help employees understand and adapt to the new CEO's vision.
Organizational
leaders
Senior managers prepare the organization for the new leader.
Organizational
leaders
The board address the interests of internal candidates.
Board of
Directors
The board allows incoming CEOs more than 3 months and up to 3 years to develop their vision
and have an impact
Board of
Directors
The board conducts formal review of the new CEO’s performance within their first 6 months on the
job.
Board of
Directors
The board decides whether internal candidates will be considered as possible successors and
communicates this decision.
Board of
Directors
The board deliberates and decides on a new successor.
Board of
Directors
The board develops accurate leadership and system profiles for the search.
Board of
Directors
The board establishes a CEO search committee.
Board of
Directors
The board finds or endorses the executive search firm.
Board of
Directors
Item
Code
The board of directors identifies the needed competencies in a new CEO
Board of
Directors
The Board of Directors or the Chairman provides a realistic overview of the current state of the
company.
Board of
Directors
The board of directors provides sufficient oversight of the new CEO.
Board of
Directors
The board selects a search firm that fits the organizational culture.
Board of
Directors
The board selects a search firm that understands and respects the organization’s mission and
vision.
Board of
Directors
The incoming and outgoing CEO should be in regular communication leading up to the
transition.
Incoming CEO
The incoming and outgoing CEO should work together regarding transition timing and priming
the organization for the new CEO’s successful entry.
Incoming CEO
The incoming CEO compares their preferred job profile to the presented opportunity.
Incoming CEO

118
The incoming CEO focuses on getting to know the organization’s people early in the transition.
Incoming CEO
The incoming CEO has a facilitated integration session with their direct staff within the first 60 days
Incoming CEO
The incoming CEO holds group meetings with organizational directors.
Incoming CEO
The incoming CEO interviews board members, executive team members, director-level staff
members, and local business and community leaders to formulate a deep understanding of the
organization’s culture, market strengths, and opportunities.
Incoming CEO
The incoming CEO meets one-on-one with administrative staff and physician leaders to get to
know them.
Incoming CEO
The incoming CEO should classify the organizational projects and initiatives as (a) continue, (b)
pause, or (c) gather more information.
Incoming CEO
The incoming CEO should develop an understanding of the reality of patient care
Incoming CEO
The incoming CEO should develop deep understanding of any volatile issues within the system
or community which may affect system’s performance and/or reputation.
Incoming CEO
The incoming CEO should ensure that many aspects of the organization remain in place for
continuity and stability.
Incoming CEO
The incoming CEO should establish critical relationships inside the organization
Incoming CEO
The incoming CEO should establish critical relationships with stakeholders outside the
organization
Incoming CEO
The incoming CEO should familiarize themselves with the search committee members before
the search committee interview using their social media and corporate websites.
Incoming CEO
The incoming CEO should meet with all key community members to meet with during the first year.
Incoming CEO
The incoming CEO should meet with all management and senior leaders within the first month.
Incoming CEO
The incoming CEO should not rush organizational change but carefully assess what needs to
change/evolve based on input from their CHRO, direct reports, and other key stakeholders (e.g.
physicians, nurses, front line talent).
Incoming CEO
The incoming CEO should research the recruiting agency, the recruiter, and their recent
placements
Incoming CEO
The incoming CEO should seek to align with the hospital’s culture
Incoming CEO
The incoming CEO should seek to understand the hospital’s culture
Incoming CEO
The incoming CEO should strive to enhance diversity through understanding the hospital’s
community, challenges around health equity, the hospital’s role in community health and research,
and staff and leadership diversity.
Incoming CEO
The incoming CEO should use their network to gain attention from the search committee.
Incoming CEO
Item
Code
The incoming CEO understands their own preferred job profile, separate from the presented
opportunity.
Incoming CEO
The outgoing CEO adopts a consultative rather than directive attitude toward the incoming CEO.
Outgoing CEO
The outgoing CEO adopts a consultative rather than directive attitude toward the incoming CEO.
Outgoing CEO
The outgoing CEO creates a list of organizational projects and initiatives to share with the
incoming CEO
Outgoing CEO
The outgoing CEO demonstrates confidence in and satisfaction with the new CEO to internal
and external stakeholders.
Outgoing CEO
The outgoing CEO identifies executive search firms for the board to consider enlisting to find a
new CEO.
Outgoing CEO
The outgoing CEO is fully out of the organization at the time the incoming CEO starts the
position.
Outgoing CEO

119
The outgoing CEO personally informs key board members and organizational staff of the
impending transition.
Outgoing CEO
The outgoing CEO refrains from asking organizational stakeholders how things are going with
the new CEO after the transition.
Outgoing CEO
The outgoing CEO should be part of the search committee.
Outgoing CEO
The outgoing CEO should connect the incoming CEO key internal and external stakeholders.
Outgoing CEO
The outgoing CEO should review all steps that a transition may require.
Outgoing CEO
The outgoing CEO, in cases of voluntary turnover, confirms a personal readiness to leave.
Outgoing CEO
The outgoing CEO, through conversations with the incoming CEO, explains their current
activities and preparations for the transition.
Outgoing CEO
The search committee keeps the board informed and involved throughout the process of finding
possible succession candidates.
Board of
Directors
Summary
The purpose of this study was to identify best practices for CEO transitions at large
hospital systems during times of significant multidimensional change. To do so, a Delphi
approach was used wherein 50 CHROs who had experience with CEO transition within large
hospital systems were invited to complete a three-round survey. Round 1 presented 75 items to
respondents and 34 (45%) achieved consensus. Respondents additionally noted 15 more critical
items to evaluate. In Round 2, 56 items were presented, and 35 (37.5%) reached consensus,
yielding an overall consensus on 69 of the total 90 critical items (77%). In Round 3, 21 items
were presented, and 14 (67%) reached consensus. Across the three rounds, 83 of the total 90
critical items (92.2%) had reached consensus, which exceeded the threshold needed
(85%) to demonstrate stability.
Research Question 2 examined whether a broader framework existed for CEO transition
in large hospital systems during times of multidimensional change. Answering this research
question required further reduction of the 83 consensus items using thematic analysis. The 83
items were organized into seven themes: CHRO, Board of Directors, Outgoing CEO, Incoming
CEO, Organizational leaders, Multiple stakeholders, and External supports. Two doctoral-level
peer reviewers verified the analysis upon their review. The next and final chapter provides a
discussion of the findings.

120

121
Chapter 5: Findings
Summary of the Study
Healthcare is the fastest growing industry in the United States and globally (Bureau of
Labor Statistics, 2022; Schiavone & Ferretti, 2021). Economists forecast that as the population
grows and life expectancy increases, the healthcare sector will continue expanding to meet
consumer needs domestically and globally (Bureau of Labor Statistics, 2022; Vogenberg &
Santilli, 2019). Aging populations will lead to increased demand for healthcare services, which is
a key factor that will contribute to growth in the sector (Dormont et al., 2010; Rowe et al., 2016;
Swanson, 2022).
In 2021, the global healthcare industry was worth $12 trillion. In the United States, the
healthcare sector reached $4.1 trillion (Insider Intelligence, 2023). The spending accounted for
20% of the U.S. GDP in this time period. Healthcare is a complex massive industry that accounts
for 20% of the United States' gross domestic product in 2020 (Insider intelligence, 2023; Keehan
et al., 2020). Industry projections suggest that the healthcare market will reach $6.2 trillion by
2028 (Gebreyes et al., 2021; Hartman et al., 2020).
Healthcare is economically important to the U.S., given the annual wages for clinician
occupations (surgeons, physicians, or registered nurses) exceed $75,000, which is higher than
the median annual wage of $45,760 for all occupations in the economy (Bureau of Labor
Statistics, 2021, 2022). Consideration of the supply of healthcare professionals to fill the jobs is a
gap that needs to be addressed by chief executives at a time when the availability of the labor
pool to fill openings is widening. As the industry faces supply and demand clinical talent
imbalance, a leadership imperative emerges (Gilmore, 2003)
According to the Bureau of Labor Statistics (2022), employment in the healthcare sector
will grow by 16% between 2020 and 2030. The growth projection will add 2.7 million new jobs,
making healthcare the fastest growing occupation than the average of all occupations combined

122
(Insider Intelligence, 2023; Keehan et al., 2020 ). Simultaneously, staff shortages remain at the
top of the list of concerns for chief executives, combined with operational challenges requiring
change while striving to maintain profitable growth to support the mission of the organization.
Between 2000 and 2030 the US confronts a shortage of clinicians: up to 122,000 physicians,
500,000 registered nurses, and more doctors near retirement age of 65 in the next decade.
A stabilized workforce is a primary focus of hospital chief executive officers (CEOs), with
94% citing staffing shortages and the lack of RNs as the predominant concern (Advisory Board,
2022; Figueroa et al., 2019). The American Hospital Association (2021) reported approximately
1.7 million people resigned from their healthcare positions which is an estimated loss of 20% of
its workforce and 30% of nurses (AHA, 2021; Delaney et al., 2021; Gazelle, 2022). Few
industries have experienced the magnitude of a mass exodus of workers as healthcare which is
important because of the industry’s impact on occupations and the health of the nation.
Employment shortages in the field remain at 80,000 jobs, a figure that has persisted since
February 2020 (AHA, 2021). Hospital CEOs are called on to provide strategic direction,
determine priorities for multiple stakeholders and create commitment across the system that
address priorities that contribute to addressing challenges (Figueroa et al., 2019; Reich et al.,
2016; World Health Organization, 2007).
As significant and problematic general turnover is in the healthcare workforce,
executivelevel resignations pose an even more serious threat to the industry. Research by
Challenger, Gray & Christmas, Inc. (2022) indicates that 46 CEOs left their roles in the first half
of 2022.
CEO turnover increased by 53% in the largest publicly traded corporations between 1995 and
2001 as CEO tenure declined from 9.7 years to 7.3 years during the same period of time (Lucier
et al., 2002). As shown in Figure 1, executive-level attrition is a growing problem.

123
Purpose
The purpose of this study was to identify organizational practices for CEO transitions at
large hospital systems during times of significant multidimensional change. In this study, a large
hospital system was defined as a multi-hospital, multi-region institution that employs more than
25,000 individuals. Multidimensional change was defined as volatile, complex, uncertain, and
ambiguous conditions that ignite social, economic, and workforce shifts within and outside the
organization.
More broadly, the study’s aim was to offer insights to organizations that wish to improve the
success of CEO transitions, especially during times of multidimensional change.
The following research questions were addressed in this study:
1. What are the most important practices for CEO transition in large hospital systems
during times of multidimensional change?
2. Is there a broader framework for CEO transition in large hospital systems during times
of multidimensional change that could be arrived at by further reduction of the data?
Significance
This study is anticipated to produce needed insights about how to effectively navigate
CEO transitions. When these transitions are done well, organizations prepare a new leader with
a change agenda, and the leader is better equipped to turn it into power dynamics on how the
culture influences a strategy shift or what cultural changes will be necessary to support the
strategic imperatives (Ciampa, 2016; Dotlich, 2016; Watkins, 2003). Further, successful
transition pathways establish foundations for productive relationships between key stakeholders,
the CEO, and board members (Ciampa, 2016).
Methods
A Delphi approach was used to answer Research Question 1. In this approach, 50
CHROs who had experience with CEO transition within large hospital systems were invited to

124
complete a three-round survey. Round 1 presented 75 items to respondents and 34 (45%)
achieved consensus. Respondents additionally noted 15 more critical items to evaluate. In
Round 2, 56 items were presented, and 35 (37.5%) reached consensus, yielding an overall
consensus on 69 of the total 90 critical items (77%). In Round 3, 21 items were presented, and
14 (67%) reached consensus. Across the three rounds, 83 of the total 90 critical items (92.2%)
had reached consensus, which exceeded the threshold needed (85%) to demonstrate stability.
Research Question 2 examined whether a broader framework existed for CEO transition
in large hospital systems during times of multidimensional change. Answering this research
question required further reduction of the 83 consensus items using thematic analysis. The 83
items were organized into seven themes: CHRO, Board of Directors, Outgoing CEO, Incoming
CEO, Organizational leaders, Multiple stakeholders, and External supports. Two doctoral-level
peer reviewers verified the analysis upon their review. The next and final chapter provides a
discussion of the findings.
This chapter provides a discussion of the findings discovered through the data analysis
for each research question. Following the findings, this chapter discusses the implications of the
study, the application of the research through the introduction of Bailey Model for Successful
CEO Transition, and recommendations for future research.
Research Question 1: Organizational Practices for Chief Executive Transition in Large
Hospital Systems During Times of Multidimensional Change
Key Factors
In answer to Research Question 1, three key factors emerged as critical from the study
for effective CEO transition in large hospital systems: (a) conducting an effective executive
search; (b) supporting, guiding, and monitoring the new CEO; and (c) informing and leading the
organization through the transition, using an effective change plan. Based on panelists’
responses, the six main constituents to the transition (i.e., the board; CHRO; outgoing CEO;

125
incoming CEO; and executives, senior leaders, and managers) all play unique responsibilities
relative to these three factors.
Role of the board. Critical items for the Board of Directors included (a) outlining and
overseeing the search a new CEO, such as selecting a search firm that understands and
respects the organization’s mission, vision, and culture as well as establishing a CEO search
committee; (b) outlining the parameters for the search and selecting the successor, such as
identifying the needed competencies in a new CEO, developing accurate leadership and system
profiles for the search, deliberating and deciding on a new successor, and deciding whether
internal candidates will be considered as possible successors and communicates this decision;
and (c) informing and overseeing the new CEO, such as providing a realistic overview of the
current state of the company and sufficient oversight of the new CEO, and evaluating the new
CEO in an appropriate time frame.
These findings are similar to extant literature, which emphasized that the board must
shepherd the process of the successor’s transition which begins with preparation, followed by
serving as a sounding board and providing feedback and advice (Schepker et al.; 2018; Tuomala
& Yeh, 2018). During preparation, boards seek to understand the requirements for success that
will lead to a clear path on resources and constraints that will need to be navigated for an
effective leadership transition (Najipoor-Schuette & Patton, 2018). The board needs to hold
incumbent CEOs accountable to performance and offer the right amount of oversight and
guidance (Dierickx & McGill, 2007).
Role of the CHRO. The CHRO plays three primary roles during the transition, including
acting as process consultant for the transition, coaching and counseling the incoming CEO, and
leading the organization through the transition toward organizational health and performance by
assuring ample communication and integration. Related to being a process consultant, the
expert panel emphasized the importance of implementing a succession planning framework,

126
serving as an internal advisor to the outgoing CEO, and coordinating and advising on the
transition process. Additionally, CHROs support incoming CEOs by helping them learn new
perspectives, adopt new behaviors, and offering support for their experiences of anxiety, stress,
or alienation. CHROs also serve in fundamental ways to support organizational health and
performance throughout the change, including helping the new CEO improve functioning of the
senior team, identifying and addressing organization culture issues, assuring the board remains
involved as a sounding board and advisor to the incoming CEO, developing and implementing a
well-developed communications strategy, and creating a transition management team, managing
administrative aspects of the change.
Extant literature similarly emphasized that CHROs play significant roles in ensuring CEO
transitions (Ciampa, 2015). Several areas in which the CHROs can help senior transitions
include serving as an internal advisor to the outgoing and incoming CEO; managing
administrative aspects of the change; facilitating communication between the board and the
senior managers and being instrumental in assisting the new CEO to strengthen ways the senior
team works well together (Ciampa, 2015; Meinert, 2015). The CHRO also is responsible for
coordinating the process and acting as an internal advisor to the process (Dierickx & McGill,
2007). Due to the gap that existed in the literature on the instrumental role chief human
resources officers play in transitioning CEOs, the present study offered unique and valuable
insights.
Role of outgoing CEO. Panelists’ responses indicated the importance of the outgoing
CEO equipping and endorsing the new CEO while making sure they themselves are exiting the
organization completely and expediently. To effectively equip the new CEO, the outgoing CEO
should review all steps that a transition may require; create a list of organizational projects and
initiatives to share with the incoming CEO; and explain to the incoming CEO their current
activities and preparations for the transition. To endorse the new CEO, the outgoing CEO should

127
connect the incoming CEO key internal and external stakeholders, refrain from asking
organizational stakeholders how things are going with the new CEO after the transition,
demonstrate confidence in and satisfaction with the new CEO to internal and external
stakeholders, and adopt a consultative rather than directive attitude toward the incoming CEO.
To assure they are leaving completely and expediently, panelists agreed that outgoing CEOs
should confirm their personal readiness to leave and be fully out of the organization at the time
the incoming CEO starts the position, and personally informs key board members and
organizational staff of the impending transition. Limited discussion was found in the available
researcher about the role of outgoing CEOs in the transition. It is likely that this limited attention
to the outgoing CEO is because a proportion of CEO transitions are involuntary. In such cases,
the involvement of the outgoing CEO would naturally be limited.
Role of incoming CEOs. Incoming CEOs, according to panelists, are responsible for a
large number of activities to ensure the success of the transition. Objectives in this process from
the viewpoint of the incoming CEO include carefully assessing the organization and community,
building relationships with all stakeholders, and formulating an effective plan for their leadership.
Activities related to assessment include such things as understanding the hospital, its culture, its
larger community, the hospital’s role in its community, and the hospital’s market realities.
Panelists agreed that the incoming CEO should not rush organizational change but carefully
assess volatile issues, what needs to change, and what needs to stay the same, based on input
from their CHRO, direct reports, and other key stakeholders.
Relationship building was a centrally important element of the incoming CEO’s tasks,
according to panelists. Specific activities included holding a facilitated integration session with
their direct staff within the first 60 days, meeting with all management and senior leaders within
the first month, meeting with all key community members to meet with during the first year and
establishing critical relationships inside and outside the organization. Formulating an effective

128
plan for their leadership includes working with the outgoing CEO regarding transition timing and
priming the organization for the new CEO’s successful entry; being in regular communication
with the outgoing CEO leading up to the transition; and classifying the organizational projects
and initiatives as (a) continue, (b) pause, or (c) gather more information.
Examination of literature on CEO transition revealed that the new leader holds the
ultimate responsibility for directing the transition process and achieving success (Dierickx &
McGill, 2007). Birshan et al. (2016) reported as many as 74% percent of U.S. leaders think they
are unprepared for their new CEO roles (Paese & Wellins, 2015). Over 402 CEOs from 11
different countries were surveyed admitted they were not fully prepared for the personal and
interpersonal aspects of the transition and the role (Najipoor-Schuette & Patton, 2018). In the
study, 29% of the CEOs reported that their organization appropriately supports new leaders
(Najipoor-Schuette & Patton, 2018). The tertiary responsibility of transitioning is the role that the
chief executives themselves play in their transition. In the study of CEOs across 11 countries,
79% agreed with the statement that they needed to transform themselves as well as the
organization. Transitions at the top are repeatedly reported to fail when major players are
unprepared, ignore, or underestimate the critical complexities of the process. Ciampa and Dotlich
(2015) explain the confluence of two factors that contribute to transition complexity: (a)
adjustments required by the key constituents and interactions between them: the sitting CEO, the
board, senior leaders, and the CHRO and (b) systemic organizational adjustments associated
with the transition: cultural, political, operational and strategical.
Role of executives, senior leaders, and managers. Panelists ranked the involvement
of executives, senior leaders, and managers as important to the transition, as these instrumental
stakeholders support employees in following the new CEO’s vision and they also help adjust the
organization as needed. These individuals also need to be open to the new CEO’s ways of doing
things, especially if those differ from how things have been done up to that point in the

129
organization. Similarly, Dierickx and McGill (2007) asserted that senior managers must prepare
the organization for the new leader and help the organization’s employees, structure, and
processes adapt to the new leader’s vision.
Panelists also stressed that multiple stakeholders involved in the transition need to
engage in effective collaboration before, during, and after transition. Panelists’ ratings also
indicated the importance of developing mutual trust and build common understanding about the
organization’s current and future state through ample communication between board, new CEO,
senior leadership and executives. Activities to support this objective involve executive team
members (a) creating a description of their division, direct reports, recent accomplishments, and
current projects to share with the incoming CEO and (b) creating a list of suggested introductory
tasks for the new CEO to consider during the first 90 days on the job. The board, executive
leadership, and incoming CEO also should establish clear business goals and clear
understanding of the delegation of authority for the CEO role.
While panelists agreed that the outgoing and incoming CEO collaborate and
communicate to promote smooth transition, they also concurred that the overall process and
amount of communication between outgoing and incoming CEO should be based upon the
nature of the departure and business needs. Specific activities that can aid this effort concerns
the outgoing CEO spending time with the incoming CEO to introduce them to the local
community and key stakeholders.
Circumstantially, the outgoing CEO and other key constituents would be involved in the
transition of the new CEO. Transition management teams provide a crucial role in the
overarching health of the organization during a time of significant change (Ciampa & Dotlich,
2022). Included in this group are representations from multiple stakeholders that include
perspectives from patients, community partners, frontline leaders, and different dimensional
diverse voices from within the organization’s workforce (Carriere et al., 2009; Nazemian, 2022).

130
Transition management teams play a crucial role in sustaining the organizational health during
times when there is flux and a need of strong strategies, as well as high talent engagement.
Role of external supports. Panelists noted that external support resources can be
instrumental in supporting the success of the CEO transition. To effectively carry out these roles,
panelists agreed that various resources could support the new CEO before, during, and after the
transition. Specific activities include the search firm or recruiter helping the incoming CEO
prepare for the interview with the search committee, a CEO boot camp being arranged to quickly
orient the new CEO, and an external executive coach helping the incoming CEO with transition
and integration matters. No related extant research was found related to the role of these kinds
of external supports, although it may exist.
Research Question Two
Research Question 2 examined whether there is a broader framework for CEO transition
in large hospital systems during times of multidimensional change that could be arrived at by
further reduction of the data. To answer this question, the items that had reached consensus
were examined using thematic analysis. The following sections describe the themes that
emerged from this analysis and the critical items that aligned with each theme. These themes
then were used to create a new model for guiding CEO transitions in large hospital systems,
which is described later in this chapter.
People Are Central to Transition Success
The success of executive transition within an organization during times of high uncertainty
and change is highly depended on people. Awareness of who is involved, what role they play,
and general accountabilities assigned to organizational practices are essential element. People
are characterized as primary, secondary or tertiary members in the transition based on the role
assigned to their function. Incoming CEO, board of director and CHRO have shared roles and
serve as the tripartite members who navigate the organizational practices of setting vision,

131
communicating, planning for succession, engaging all stakeholders and monitoring the
organizational performance. In this model, these are the three primary players identified as the
main contributors to the transition.
Multiple stakeholders need to be involved to adequately address people issues. Those
stakeholders include the board of directors, incoming CEO, CHRO, outgoing CEO, community
constituents, organizational leaders, external support expertise, such as executive search firms
and executive coach, as well as consumers and patients. It is also important to provide people
with a clear understanding of their roles and responsibilities throughout the entire transition.
Clarity of members, roles and practices should be established at the outset when it is evident
that transition will occur.
People are fundamental to the organization’s continual operation during the transition.
The role of people in an executive transition is critical given the multivariant impacts. For
example, anticipated outcomes: leaders’ morale degradation, a ripple effect of senior leader exits
which elevate succession planning or replacement needs, performance degradation when there
is a void or stagnation of fulfilling strategic plans or change in services to patients and
communities.
One of the most important roles of the people is communicating effectively with all
stakeholders. It is essential to keep people informed of the transition elements taking place with
a focus on message relevancy to each audience. A few examples, town hall informational
sessions, one-on-one conversations with organizational leaders, written communications.
Communicating includes both internal and external stakeholders. For example, customers,
community constituents, organizational leaders, internal and external members contribute to the
transition process.

132
Accelerating and Keeping the Momentum of the Transition is Essential
People acceleration during transitions refers to the deliberate, proactive efforts taken by
the primary players to ensure that all stakeholders are equipped and prepared to support the
incoming CEO, along with the changes necessary for the transition. It is about advancing change
at a pace that keeps forward momentum toward a intended outcome or goal.
The acceleration step involves strategies and initiatives designed to keep the transition of
the incoming CEO into the organization while minimizing potential negative impacts on employee
morale, engagement and productivity. One of the key aspects of people acceleration is
communication. Clear and consistent communication facilitates employees’ level of awareness of
the changes underway and what can be expected. Communication can assist in reducing
uncertainty, build trust and articulating the vision can establish confidence in the future with an
incoming CEO.
Boards accelerate transitions through oversight of the CEO transition and promotes the
efficient and effective use of resources to accelerate the pace of change. Incoming CEO leads
acceleration in the shift in the strategy, culture, leadership, or other significant factors.
Setting the pace of the transition is earmarked by the Board setting timelines that are
communicated and supported by the CHRO and organizational leaders. External supports also
contribute to accelerating the transition. Timely candidate identification and assistance provided
to the Board of Directors in naming the incoming CEO is one way that transition accelerating is
aided through people. Coaching or consulting support for the incoming or outgoing CEO
accelerates transitions by identifying factors that either support or derail progress. Another
example of accelerating a transition is the early identification of succession needs of
organizational leaders to minimize or mitigate business disruptions during times of change.
Building relationships is another aspect of people acceleration. The incoming CEO must
establish relationships with multiple stakeholders within the organization to understand the

133
culture, strengths, weaknesses, and opportunities. Similarly, organizational leaders’ establishing
a relationship with the incoming CEO to build trust so that the pace of adoption of the vision
moves forward.
Overall, people acceleration during an executive transition is about ensuring that the
organization's people are fully prepared and equipped to support the incoming CEO's and the
changes that come with the transition. Deliberate and proactive steps to build relationships,
communicate effectively enable organizations to accelerate the integration process and minimize
negative impacts on morale engagement and productivity.
Need for Transition From Former to Modified Practices
Focusing on organizational practices that support ushering in a change in leadership of
an organization. In essence, transitions in the PATT model is the bridge from the existing
organizational practices to mew or modified practices.

