


1
Chapter 1: Introduction to the Study
Introduction
The field of radiation oncology (RO) involves using high-energy radiation
to target cancer lesions while sparing the surrounding healthy tissues (American
Cancer Society, 2018). The field experienced rapid growth in the early 2000s,
with the development of innovative techniques, such as intensity-modulated
radiation therapy (IMRT). This technique allowed clinicians to “bend” radiation
and customize each patient treatment by creating concave dose distributions that
spare healthy tissues (Chen, 2014). This rapid growth paved the way for an array
of other innovative techniques, such as advances in imaging and oncology
informatics (Chetty et al., 2015).
Many fields in health care struggle to implement innovative techniques
such as these in the clinical workflow. The adaptation of innovation within
discrete organizations is well understood, yet how the entire health care system
transforms to accept health care innovations and thus improve population health is
abstruse (Parston et al., 2015). Morris, Wooding, and Grant (2011) estimated that
it takes 17 years for an innovation to spread throughout the health care industry.
This time lag is more prominent in low-resource settings, leading to inequalities
(Keown et al., 2014). In RO, differences in treatment modalities have a notable
impact on cancer survival, yet centers offering innovative treatment techniques
are inaccessible to part of the population, leading to health care disparities (Chen,
2014).

2
Jacobs et al. (2016) investigated the innovations adopted in Dutch RO
centers. The authors found that in the Netherlands, RO centers implement on
average 12 innovations per year. In reviewing the literature, there are no current
studies quantifying the diffusion of innovation in RO across the United States.
The purpose of this study was to fill this gap in the literature. University
affiliation and urbanicity were investigated as possible predictors. The role of
medical physicists was also investigated by using an array of demographic
parameters and context-specific antecedents to develop a predictive model for
accessibility of innovative services in RO in the United States.
There are numerous examples of innovative practices, policies, and
products that improve health care provision (Darzi & Parston, 2013). The
methods by which an innovation gains momentum and diffuses (or spreads)
throughout a specific population or social system over time is typically referred to
as diffusion of innovation (Rogers, 2003). Diffusion is a passive spread, as
opposed to dissemination, which is active (Rogers, 2003). Public health
researchers often overlook the possible lack of diffusion of innovation in efforts to
improve population health (Darzi & Parston, 2013). Developing a tool to measure
innovation in RO can be the first step in developing a predictive model for
improving the diffusion of innovation in the field. This quantitative assessment
may contribute to the improvement of accessibility and quality of RO services
across the United States, improve cancer outcomes, and thus contribute to positive
social change.

3
Background
Innovation and its implementation are actively studied across many
disciplines. The implementation of innovative methods in health care and how
these methods reach the general population is an active field of research. For
example, the researchers who undertook the Global Diffusion of Health Care
Innovation study investigated the effects of rapid adoption of innovations on
public health worldwide (Darzi & Parston, 2013). Parston et al. (2015) identified
three phases of change management: (a) creating a climate for change by having
vision, strategy, and a specific agency to promote diffusion, transparency, and
communication channels; (b) engaging and enabling the whole organization by
having incentives and rewards; and (c) implementing and sustaining by making
time and space for learning. The authors emphasize that implementing change in
health care is both an art and a science (Parston et al., 2015). Parston et al.
explored quantitative and qualitative parameters that affect innovative technique
implementation in a variety of socio-demographic environments. In health care,
the adoption of innovative techniques is not an academic exercise, it can save
lives.
Clinical effectiveness in RO is by necessity retrospective, and there have
been no long-term clinical trials for the majority of innovative techniques used in
health care. The adoption of new techniques is primarily based on reasonable
theoretical long-term benefits (Chen, 2014). Assessing cancer survivorship as a
whole using big-data analyses and defined value is still ongoing (Nardi et al.,

4
2016). Smith et al. (2017) discussed the definition of the value of innovation
implementation from multiple stakeholders and how scientific evidence enters the
marketplace of RO. Value can mean (a) societal value, such as lost wages, lost
productivity, and willingness to pay; (b) care value, such as disease control,
quality of life and long-term theoretical benefits; or (c) system value, such as
incremental costs, budget impact, and affordability. Nardi et al. (2016)
investigated the value of comprehensive cancer centers designated by the National
Cancer Institute (NCICCC). The authors found that for specific cancers, such as
hepatobiliary, lung, pancreas, gastric, breast, cervical, oral, and colorectal cancer,
patients had a 20-30% higher 5-year survival when treated at an NCICCC (Nardi
et al., 2016). NCICCCs are disproportionally located in the Eastern United States,
which means that for many patients, it is simply not an option to receive treatment
at these facilities (Nardi et al., 2016). Additionally, many health care plans do not
cover services at university hospitals or NCICCCs at all (Nardi et al., 2016). The
majority of Americans, therefore, do not have access to centers that provide better
cancer outcomes, either because of geographical limitations or because their
insurance does not cover treatment at institutions with proven better outcomes
(Nardi et al., 2016). Lack of access to care is one of the many challenges in the
contemporary United States, and there are no existing studies addressing this issue
in the field of RO, according to the review of the literature. This study measured
the accessibility of innovative services in RO in the United States and attempted
to fill this literature gap.

5
Problem Statement
The field of RO has experienced rapid growth in the past 25 years, with
technological advancement as the driving force. The need for innovation in health
care is broadly accepted as necessary, with current innovation considered
insufficient at this point (Parston et al., 2015). Implementing innovative
techniques requires significant resources, and community hospitals are trailing
behind (Nardi et al., 2016; Pfister et al., 2015). Fragmented data on innovation are
available from vendors and professional societies such as the American College
of Radiology (ACR) and the American Society for Radiation Oncology
(ASTRO), but there has been limited analysis of the barriers to developing and
implementing new technology in RO (Mayo et al., 2016).
The study of the mechanism by which innovations spread geographically
and across time is of particular interest in health care and is an active field of
research. These diffusion patterns are explained using various theoretical models,
one of which is the diffusion of innovation theory, as described by Rogers (2003).
Diffusion patterns can be assessed by sampling a variety of stakeholders. In this
study, the problem of diffusion of innovation was addressed from the point of
view of medical physicists (MPs), who are responsible for the acceptance,
commissioning, and implementation of innovative techniques in RO. MPs are
emerging into leadership positions in RO facilities across the United States, not
only as technical experts but as the leaders in quality management (Delis et al.,
2017). In the study, MPs were evaluated as the adopters of innovations in RO.

6
MPs are not passive recipients of innovation: They seek innovations, assess them,
find meaning in them, develop positive or negative opinions about them, gain
experience with them, complain about them, work around them, modify them, and
circle back to the beginning, beginning the process once again (Rogers, 2003).
The main adopter categories may be broadly defined as innovators, early
adopters, early majority, late majority, or laggards (Rogers, 2003). There is
extensive literature on how cognitive and social psychological antecedents affect
the individual’s adoption (Greenhalgh, Robert, Macfarlane, Bate, & Kyriakidou,
2004). The psychological antecedents included in this study were motivation,
appreciation, self-efficacy and leadership style.
As discussed in the “Background” section, innovative techniques are not
accessible equally by all patients, as they are typically available at higher rates in
university hospitals or urban centers (Pfister et al., 2015). This lack of access is
directly related to inferior survival outcomes (Nardi et al., 2016). Jacobs et al.
(2016) studied the implementation frequency of innovative techniques in the
Netherlands and found a wide range across all centers. They found differences
between university and community hospitals and emphasized the lack of national
recommendations for prioritizing innovations, setting goals, and societal
interventions as long-term solutions (Jacobs et al., 2016). There is a literature gap,
however, on the extent of accessibility of innovations in RO in the United States
and its impact on public health. The accessibility of innovative services in RO

7
across the United States as an indicator of public health outcomes was further
assessed in this study by exploring the role and involvement of MPs.
Purpose of the Study
The purpose of this study was to investigate the accessibility of innovative
services in RO in the United States and assess possible diffusion patterns. These
patterns were used to create a predictive model of the factors that may affect MPs’
role in the diffusion of innovation. An Internet-based survey was conducted with
a convenience sample of MPs practicing in RO in the United States. A
quantitative cross-sectional analysis of survey data was conducted to gain insight
on the accessibility of Food and Drug Administration (FDA)-approved innovative
techniques in RO. The dependent variable was innovation score, defined as the
number of techniques available to or purchased by a department divided by the
number of techniques used clinically, weighed by partial implementation factors.
Independent variables were geographic location; practice details (university
affiliation, reporting structure, size of physics group); demographics (age, gender,
DABR status, residency status, meeting attendance, and education level); and
context-specific psychological antecedents (motivation, appreciation, and
leadership).
Research Questions and Hypotheses
The research questions (RQs) and hypotheses were as follows:
RQ 1: What are the differences in accessibility to innovation in RO based on
location and type of practice in the United States?

8
RQ 2: What are the statistically significant factors (demographics, practice details,
context-specific psychological antecedents) that predict the accessibility to
innovation in the RO clinic?
RQ 3: What are the statistically significant barriers that MPs practicing in RO in
the United States face in implementing innovations?
Hypothesis 1a
H1a0: There is no statistically significant difference in accessibility to
innovation in RO between university and non-university hospitals.
H1a1: There is a statistically significant difference in accessibility to
innovation in RO between university and non-university hospitals.
Dependent variable: innovation score (continuous).
Independent variable: university affiliation (categorical, two levels: has
university affiliation, does not have university affiliation).
Hypothesis 1b
H1b0: There is no statistically significant difference in the accessibility to
innovation in RO between metropolitan and nonmetropolitan hospitals.
H1b1: There is a statistically significant difference in accessibility to
innovation in RO between metropolitan and nonmetropolitan hospitals.
Dependent variable: innovation score (continuous).
Independent variable: urbanicity (categorical: metropolitan,
nonmetropolitan).

9
Hypothesis 2
H20: There are no statistically significant factors predicting innovation
score.
H21: There are statistically significant factors predicting innovation score.
Dependent variable: innovation score (continuous).
Independent variables: reporting structure, size of physics group, age,
gender, DABR status, residency status, meeting attendance, education
level, leadership (categorical), appreciation, and motivation (continuous).
Hypothesis 3
H30: There are no statistically significant barriers affecting innovation
score.
H31: There are statistically significant barriers affecting innovation score.
Dependent variable: innovation score (continuous).
Independent variables: barriers (continuous).
Theoretical Framework for the Study
“Evidenced-based decision making” is a frequently used phrase in health
care fields, yet research shows a disconnect between strong scientific support and
diffuse clinical usage. Pedersen (2015) discussed that health care fields are
different in their adoption of innovations due to contextual sense-making:
engagement, materialization and scientification of innovations provides meaning
to users. Wisdom, Chor, Hoagwood, and Horwitz (2014) defined innovation
adoption as a complex quality improvement intervention and categorized the

10
mechanistic constructs for the individual to accept innovation and implement it in
their organization; adoption of innovations is a dynamic process. The unit in this
study was MPs. The MPs, as individuals, accept or reject innovations and in turn
facilitate their RO departments in fully utilizing innovations. The assessment of
the role the MPs play in the diffusion of new products and practices across the
modern RO clinic health care system in the United States was studied by
measuring diffusion patterns of these products and practices. Diffusion is defined
as “the process in which an innovation is communicated through certain channels
over time among the members of a social system” (Rogers, 2003, p. 5). Rogers
developed the diffusion of innovation theory in 1962 (Rogers, 2003). The theory
is based on principles of communication of participants in a social system
(Rogers, 2003). There are four elements that influence diffusion: the innovation
itself, the communication channels, time, and the social system (Rogers, 2003).
In health care, clinical practices are often labeled evidenced-based, yet
there is a significant gap between clinical practice and recent scientific
developments. Health care innovations are not simple to implement in most
clinical settings and require differential resource allocation across multiple levels
of the organization. Omachonu and Einspruch (2010) developed a health care-
specific conceptual framework involving various stakeholders such as physicians
and caregivers, patients, organizations, and regulatory agencies. Physician
acceptance, the complexity of innovation, partnerships and collaboration,
organizational culture, regulatory acceptance, and organizational leadership all

11
contribute to the probability of acceptance of an innovation (Omachonu &
Einspruch, 2010). In the field of RO, there has been a broad discussion on how
technological advances can lead to improved patient outcomes, and stakeholders
are encouraged to embrace innovation (Chetty et al., 2015). Yet there is no
framework to quantify or improve the accessibility of innovative techniques. For
this study, accessibility of innovative RO services was measured using the
innovation score, as described in the “Nature of the Study” and “Definitions”
sections that follow.
Nature of the Study
This study was a quantitative numerical assessment of the extent of
accessibility of innovative techniques across the United States. The dependent
variable was the accessibility of innovative techniques: how many end-users have
each technique, how many of them use it, and to what extent. It is common to
have partial implementations of innovative technologies (Smith et al., 2017). For
participants who did not use techniques that were available to them, influencing
variables were investigated. Correlating the accessibility with the type of hospital
revealed if community hospitals were trailing behind. Reviewing the zip code
entries relative to the innovation score revealed if rural areas were indeed less
likely to utilize innovative techniques. Age, gender, DABR status, residency
status, meeting attendance, and education level of the MPs and correlation with
the availability of innovative techniques revealed how these factors affect

12
innovation. This information is pertinent to overcoming real and perceived
barriers in technology implementation in RO.
In 2018, the AAPM directory listed approximately 7,500 members in total,
and approximately 5,500 members are listed as active in the United States (not
student, retired, associate, or corporate members) (American Association of
Physicists in Medicine, 2018). Seventy-seven percent of the membership reported
being active in RO (American Association of Physicists in Medicine, 2018); thus,
there were about 4,200 eligible MPs. The survey was posted on LinkedIn, the
MedPhysUSA user forum, and the AAPM Blackboard forum. The MedPhysUSA
is a listserv hosted by Wayne University. It is a highly active online community
for MPs, where surveys are frequently posted, with over 4,000 members. Users
must subscribe, and there are volunteer moderators. Unofficial surveys typically
garner an approximate 5-10% response rate and official surveys an approximate
30-35% response rate. (American Association of Physicists in Medicine, 2017)
Considering this response rate and the estimated number of AAPM members,
approximately 200 responses were expected for this survey.
Definitions
American Association of Physicists in Medicine (AAPM): A scientific and
professional organization composed of more than 8,000 scientists whose clinical
practice is dedicated to ensuring accuracy, safety, and quality in the use of
radiation in medical procedures such as medical imaging and radiation therapy
(American Association of Physicists in Medicine, 2019) .

13
Context-specific psychological antecedents: For the purposes of this study,
motivation (the internal process that makes a person move toward a goal),
appreciation (recognition), and leadership.
Diffusion of innovation: The study of the spread of new ideas and
technologies among individuals and groups (Rogers, 2003).
Diagnostic radiology (DR): The field of medicine that specializes in the
diagnosis of disease using ionizing and non-ionizing radiation (American College
of Radiology, 2011).
Intensity-modulated radiation therapy (IMRT): A subset of advanced
methods used in RO to manipulate the area of treatment and conform to the shape
of individualized tumors and spare critical organs (National Cancer Institute,
2011).
Innovation: For the purposes of this study, innovation will be broadly
defined to cover products (for example, new technology, inventions, drugs, etc.);
practices (ways of working, clinical protocols, workforce changes, etc.); and
policies (those things that regulate/influence the use of products and practices).
The idea that an innovation is “new” is relative: It is defined as previously
unknown to the relevant unit, not new on an absolute time scale (Rogers, 2003).
Innovation Score: The total score of measured innovation indicators for
product, technology, and organizational innovation. This is a continuous variable.

14
Innovation Utilization Score: The total score of measured innovation
utilization indicators for product, technology, and organizational innovation. This
is a continuous variable.
Medical oncology (MO): The field of medicine that specializes in the
treatment of malignant cancers using pharmaceutical agents (National Cancer
Institute, 2011).
Radiation oncology (RO): The field of medicine that specializes in the
treatment of malignant cancers using ionizing radiation (National Cancer Institute,
2011).
Assumptions
There are inherent assumptions for this study. As primary data were
collected, it was assumed that enough MPs will participate in the study to achieve
statistical significance or at least make the results as representative as possible. It
was also assumed that participants answered truthfully to all the questions of the
study. Further, it was assumed that MPs play a vital role in the diffusion process.
Scope and Delimitations
It is important to note the difference between availability and accessibility.
Availability of innovative techniques is undoubtedly essential. After all, if
something is not available at all, it cannot be used and implemented. Yet the
availability of innovative techniques in RO would be more of interest in
marketing studies, not public health. The focus of this study is on accessibility, in
the context of equitable distribution when taking into account demographic

15
composition, urbanicity and under-served populations (World Health
Organization, 2018).
The survey was sent to the entire database of the MedPhysUSA listserv,
the AAPM Blackboard, and also posted on LinkedIn. Only MPs practicing in RO
were included. Participants practicing in U.S. territories or internationally were
excluded. Participants with both Master’s and Doctoral degrees were included.
Participants were assumed to be fluent in English.
Limitations
Selection Bias
A possible source of selection bias is the exclusion of physicists who are
not participating in the online forums mentioned in the “Nature of the study”
section. This possible selection bias was minimized by using LinkedIn in a
snowball fashion, to attempt to reach MPs who do not participate at the
MedPhysUSA or AAPM Blackboard. Similarly, MPs in rural community
hospitals may have been too embarrassed to participate, if they feel the
technology they are utilizing is not adequate. Both of these could be a serious
source of error, as the MPs in the areas with the most need for new technology
may not participate. To minimize selection bias, results were reviewed in total and
in a weighted average from university and community centers, based on known
proportions, when needed.

16
Information Bias
One of the possible sources of information bias in this study was recall
bias. Szklo and Nieto (2014) define recall bias as inaccurate recall of past
exposure. In the context of this study, the respondents may have inaccurately
recalled the exact details of the implementation of new techniques. The recall bias
may be entangled with social desirability bias. MPs are highly skilled and highly
paid professionals, and admitting that they have something available but not using
it clinically may be ignominious. This may have influenced them to report that
they are using a technique, or that they have been using it more than what is
actually the reality. Questions were posed on a sliding scale in an attempt to make
it more likely for the respondents to answer more truthfully.
Confounding
University affiliation and urbanicity were assessed as possible
confounders for the study. All these factors may affect both the exposure and the
outcome separately, and they are not directly in the causal pathway.
Statistical Limitations
Based on the expected participant number, 5% chance of Type I error and
20% chance of type II error is reasonable. The statistical power of 80% is a
reasonable initial goal as well Type II errors, not detecting an effect that is
actually there, or false negative, have more significant social implications than
Type I errors in this study. Not detecting an under-performance in community and
rural RO centers would lead to lack of supplemental efforts from AAPM to boost

17
their utilization of new techniques. This would be a disservice to the patients as
discussed in the section below.
Significance
There is a limited ability for hospitals to purchase innovative techniques,
as RO medical devices are extremely expensive. Even though there is insurance-
based reimbursement, the capital investment is beyond reach for many hospitals.
For example, a linear accelerator costs $1.5 million to $6 million, and the
innovative techniques under consideration cost $50,000 to $500,000 (Modern
Technology, n.d.). These capital investment amounts require years of strategic
planning and significant budget amounts. Since RO treatments are delivered daily
over several weeks, patients commonly select facilities close to their area of
residence (Pfister et al., 2015). Innovative techniques provide an improvement in
survival; thus disparities in accessibility to these innovative techniques is a public
health problem.
Survival rate numbers have significantly improved over the past ten to
twenty years on the global level, and the reason is largely attributed to improved
targeting methods, through the use of innovative techniques such as IMRT
(Cancer Research UK, 2015). Providing RO care of the highest quality to all
patients by improving the utilization of innovative FDA-approved techniques can
contribute to the improvement of accessibility and quality of RO services across
the United States and subsequently improve cancer outcomes. Better health
outcomes are directly related to a gain in hours worked and an increase in

18
individual income up to 30% (Marquez & Farrington, 2013). These results are
even more pronounced in low-income settings, when health costs may be out of
pocket. Declining health costs is often a reason quoted for crossing the poverty
line (World Health Organization, 2010). Healthier people are more efficient in the
workplace, and this affects government and commercial sector alike (General
Electric, 2014). Innovative techniques are available, but may not be accessible to
all patients. There are enormous inequalities within and between nations in health
care in general and the public health effects of this at the global level are being
investigated by the Global Diffusion of Health care Innovation study (Darzi &
Parston, 2013). This public health problem is in alignment with the ninth essential
public health service to "evaluate effectiveness, accessibility, and quality of
personal and population-based health services" (Centers for Disease Control and
Prevention, 2017). There are currently no studies measuring the accessibility of
innovative services in RO in the United States. Measuring the accessibility of
innovative services in RO and developing a predictive model to offer a foundation
to improve it is a contribution to positive social change.
Summary
The National Cancer Institute (2018a) estimated that in 2018 alone, there
were 1.7 million new cancers and approximately 609,000 deaths due to this
disease in the United States. Cancer incidence in the United States is 439.2 per
100,000 people, and mortality is 163.5 per 100,000, with higher mortality in men
(196.8 per 100,000) than women (139.6 per 100,000). Mortality is highest in

19
African American men (239.9 per 100,000). Throughout their lifetimes, 38.4% of
Americans will be diagnosed with cancer, leading to $147.3 billion in national
expenditures for cancer care. As the population ages, the number of new cancer
cases per year is predicted to be 23.6 million by the year 2030. There are
quantitative demands, such as the number of cancer centers and relative staff
(Aneja & Yu, 2012; Yang et al., 2014), and the challenges of rural cancer care in
the United States is well documented, with multiple studies correlating driving
distance to RO center with treatment decisions and outcomes (Charlton,
Schlichting, Chioreso, Ward, & Vikas, 2015).
There are approximately 2,500 RO centers in the United States, 5,500
radiation oncologists, and 4,000 MPs specializing in RO (Ballas, Elkin, Schrag,
Minsky, & Bach, 2006). Little is known, however, about the different techniques
used in every RO center. While the majority of patients are treated using national
standards (National Comprehensive Cancer Network, n.d.), the guidelines provide
a wide range of options, allowing customized clinical decisions.
Even though products may receive FDA approval, little is known about
their implementation in the clinical setting. It is well demonstrated that the
majority of health care spending is due to the cost of technological innovations
(Dybczak & Przywara, 2010). In turn, there are many publications on how
specific innovations improve output, such as survival, toxicity, safety, service,
efficiency, or cost-effectiveness. In the next chapter, a literature review was
conducted on the diffusion of innovation in health care in general, and RO

20
specifically. Systematic reviews and cross-sectional studies were reviewed.
Results were thematically synthesized to the diffusion of innovations in health
care in general, diffusion of specific innovations in RO, effects of innovations on
value, effects of innovations in quality and patient outcomes, and social impact.

21
Chapter 2: Literature Review
Introduction
The purpose of this study was to investigate the accessibility of innovative
services in RO in the United States and assess possible diffusion patterns. These
patterns were used to create a predictive model of the factors that may affect MPs’
role in the diffusion of innovation in RO. From the literature review presented in
this chapter, it is evident that RO has a push-pull relationship with innovation.
Innovation is readily available, yet not extensively utilized, at least not in all
settings. For innovative technologies that are purchased as part of a package, as
well as those with no upfront costs, health care professionals appear hesitant to
undertake implementation. To some extent, the hesitancy to embrace innovation is
understandable, as outcomes have been improving using traditional techniques
(Chen, 2014; Jagsi et al., 2012; Smith et al., 2017). For practitioners in suburban
or rural areas, who are not in direct contact with opinion leaders and research
findings, it may indeed appear this way that outcomes are improving with
continuous use of traditional techniques. Even though errors leading to patient
death exist in all medical fields, in RO there are many catastrophic errors that can
occur on any day of the long treatment path, typically lasting weeks. Despite the
importance of this topic, there are currently no assessments of the diffusion of
innovation in RO in the United States. This study will contribute to filling this
literature gap.

22
The chapter begins with an overview of the literature search strategy,
theoretical foundation, and methodology used in the study. In the literature review
that follows, the theoretical foundation of the study, diffusion of innovation, and
how it applies to health care and RO are presented. Previously published
systematic reviews and cross-sectional studies were used to develop a thematic
synthesis of key literature for the review. Topics include the diffusion of
innovations in health care in general, diffusion of specific innovations in RO,
effects on value, effects on quality and outcomes, social impact, and predictive
parameters.
Literature Search Strategy
Walden University Library and Google Scholar were used to conduct
searches of the literature. Search terms included radiation oncology, oncology,
diffusion of innovation, early adopters, medicine, health care, radiology, equity,
and public health. Key words were based on key concepts in previously identified
published reviews. Diffusion of innovation is sometimes referred to by other
terms, and thus, similar key word items were also used, such as innovation,
adoption rate, new technology, and new technology accessibility. The key words
were combined in various ways using Boolean operators in context--for example,
early adopters in radiation oncology, new technology in radiation oncology,
diffusion of innovation in healthcare, new technology in radiation oncology
innovation, health equity, and accessibility to new technology. After the initial
review of the results, further parameters were identified that were considered to

23
possibly be influential. Additional searches were conducted using the following
terms: academic, academic cancer centers, university hospital, community
hospital, rural/rurality, city/urban/urbanicity, demographics, reporting structure,
employment type, appreciation, motivation, and leadership. These were combined
with innovation, adoption rate, new technology, and new technology accessibility
using Boolean operators as described. Only articles published in English were
included. The date range was limited to articles published since 2013, with the
exception of seminal works on the theory of diffusion and well-established
psychological context-specific antecedents.
The various search parameters produced over 200 results. These were
screened manually and articles were excluded when not directly pertinent.
Additional studies were identified by following the references. This step was
performed by using the “cited by” function in Google Scholar and by manually
looking up references within the selected articles, when applicable. Due to the
narrow focus on RO, the search was expanded to other fields of medicine and
health care. Studies were included when they addressed diffusion of innovation
patterns of clinical innovations in other medical fields, especially DR and MO,
which are the closest fields to RO. Results were thematically analyzed as
described in the following sections.
Theoretical Foundation
Health care practitioners have a long and beguiling history of accepting or
rejecting innovations. The basic principles of hygiene were developed from

24
Hippocratic medicine in ancient Greece. These principles may be considered
elementary today, but they were innovative at the time. They received
considerable criticism and skepticism and, to this day, are not accepted in certain
parts of the world (Tountas, 2009). More recently, the resolution of scurvy was
much delayed in the 18th century, as the British Royal Navy stubbornly refused to
accept and diffuse the practice of vitamin C supplementation. The fable may be
well known to public health practitioners, but the details of the delayed
implementation circa 1793-1800 as described by Vale (2008) paint a picture full
of political intrigue. The influence of a few forward-thinking physicians was the
catalyst needed for the widespread adoption of vitamin C against scurvy (Tountas,
2009). Public health history is full of similar examples, from the distant past until
present day.
Schumpeter (1989) described the continuous generation of innovations as
“creative destruction” (p. 83) and concluded that adaptation to innovation is the
rule, not the exception. Increasing health care costs, aging populations, and more
demanding consumers are compelling organizations to offer innovative solutions
(Herzlinger, 2006; Varkey, Horne, & Bennet, 2008). However, less than 50% of
all evidence-based practices are effectively implemented in the health care system
(Alexander & Hearld, 2011; M. Jacobs et al., 2017). Innovation implementation is
an area that needs improvement in health care in general and in RO as well.

25
Diffusion of Innovation
Rogers first introduced diffusion of innovation theory in 1962, while
studying rural sociology in the Midwestern United States and the adoption rates of
hybrid seeds in the area (Rogers, 2003). He combined over 500 studies from a
variety of fields, including anthropology, early sociology, rural sociology,
education, industrial sociology, and medical sociology, and the synthesis was his
seminal diffusion of innovation theory (Rogers, 2003). The theory has expanded
into social network analysis and is currently frequently used in communications,
marketing, development studies, health promotion, organizational studies,
knowledge management, conservation biology, and complexity studies,
particularly in the medical field and health communication studies (Rogers, 2003).
There are five stages in implementing an innovation, as described by Rogers
(2003):
1. Knowledge. The individual is exposed to an innovation for the first time
but does not have significant knowledge about the specifics of the
innovation. There is not yet any motivation from the individual to pursue
the innovation.
2. Persuasion. The individual is actively interested in the innovation and is
beginning to consciously explore related information/details.
3. Decision. The individual begins to study the advantages and disadvantages
of using the innovation and decides whether to either adopt or reject the

26
innovation. This stage is the most individualistic and thus the most
difficult to collect empirical evidence on.
4. Implementation. The individual begins to use the innovation to a smaller
or larger degree, depending on the situation. The individual also
determines their personal opinion on the usefulness of the innovation and
may research additional information on the innovation.
5. Confirmation. The individual finalizes the decision to continue using the
innovation. This stage is both intrapersonal and interpersonal,
confirmation the group has made the right decision.
The degree by which innovation is accepted by individuals depends on
both the individual’s characteristics and on the characteristics of the organization
in which the innovation is going to take place and typically follows an S-curve
(Rogers, 2003). Rogers classified individuals within a social system as being in
one of five categories:
1. Innovators. This group is willing to take risks, has the highest social
status, has financial liquidity, is social, is in touch with scientific
sources, and has frequent interaction with other innovators. They have
high-risk tolerance for adopting new technologies.
2. Early adopters. These are typically the opinion leaders among all the
categories. They may have higher social status, financial freedom,
higher education and may be more socially open than late adopters.
They are more thoughtful in adoption choices than innovators.

27
3. Early majority. This group adopts an innovation after significantly
larger amount of time than the innovators and early adopters. They
may have above average social status, contact with early adopters and
are less likely to hold positions of opinion leadership in a system.
4. Late majority. This group adopts an innovation much later than the
average participant. They view innovation with cautiously and with a
high degree of skepticism and even after the majority of society has
adopted the innovation. The Late Majority group are below average
social status, have little financial liquidity, in contact with others in
late majority and the early majority and little opinion leadership.
5. Laggards. This group is the last to adopt an innovation. Contrary to the
other categories, Laggards show little to no opinion leadership.
Individuals belonging to this group typically have a strong dislike for
change-agents. Laggards typically tend to be focused on "traditional
ways," have the lowest social status, lowest financial liquidity may
typically be older than adopters, and are in contact with only family
and close friends.
Rogers (2003) recognizes five qualities that determine the success of an
innovation.
1. Relative advantage. This is the degree to which an innovation is
perceived as better than what is currently available, relative to the
actual users, for example in terms of economic advantage, social

28
prestige, convenience, or satisfaction. If the innovation has a high
perceived relative advantage, it will get adopted at a more rapid pace.
Relative advantage is subjective and may carry a different meaning for
different individuals or groups. It depends on the particular needs and
dynamics of the user group.
2. Compatibility with existing values and practices. This is the degree to
which an innovation is perceived as being consistent with the values,
past experiences, and needs of potential adopters. If innovation is
comparable with the group's values, norms or practices, it will be
adopted more rapidly.
3. Simplicity and ease of use. This is the degree to which an innovation is
perceived as difficult to understand and use. If an innovation is simple
and easy to understand it will be adopted more rapidly than
innovations requiring increased understanding and new skills.
4. Trialability. This is the degree to which an innovation can be
experimented with on a limited basis. If innovation can be trialed out
by the individual considering it, without being bound in it, it will be
more likely that the individual will consider it.
5. Observable results. If the results of an innovation are easily visible to
users, they are more likely they are to adopt it. When the results are
clearly visible, there is lower uncertainty and increased peer discussion
of a new idea, as more people seek information about the innovation.

29
According to Rogers (2003), these five qualities determine between 49 and 87%
of the variation in the adoption of new products.
Reinvention is one of the leading principles in the diffusion of innovation.
The success of an innovation is highly dependent on how well it evolves to meet
the needs of the more risk-averse individuals in a population. The innovation does
not have to be new in an absolute sense; it just has to be new to the individual.
Organizational and Personal Antecedents
Organizational and personal characteristics dynamically influence the
outcome of successful innovative behavior. The organizational and personal
constructs related to innovation are increasingly investigated across many
research fields such as information systems, psychology, organizational and
management science and multidisciplinary science (Najaftorkaman, Ghapanchi,
Talaei-Khoei, & Ray, 2015). The organizational constructs affecting innovation
were summarized by Wisdom et al. (2014) to be absorptive capacity, leadership
style, networking, culture, size and structure, social climate, social network,
training readiness and effort, and traits and readiness for change. The individual
characteristics affecting innovation were summarized by Wisdom et al. (2014) to
be affiliation with organizational culture, attitudes, motivation, readiness for
improvement and reward, feedback on execution and fidelity, awareness, social
networking, knowledge/skill, competence, and demographic factors. Context-
specific psychological antecedents, such as appreciation, motivation, and

30
leadership are also well-studied to influence the individual’s response to
innovation (Greenhalgh et al., 2004; Pedersen, 2015; Wisdom et al., 2014).
Adoption and Diffusion of Innovation in Health Care
The adoption and diffusion of innovative services in health care is distinct
from other fields. The lack of effective implementation of innovations in health
care affects the lives of patients. Reinhardt, Hietschold, and Spyridonidis (2015)
analyzed Roger’s classical diffusion of innovation framework and how it pertains
to health care. The authors investigated the five qualities that determine the
success of an innovation mentioned before and found them to be valid in the
health care setting: relative advantage translates to focus on “hard” numbers,
compatibility translates to leaving non-core processes unchanged, complexity
translates to using easy-to-use innovations and shifting the point of care,
trialability translates to making parts of the innovation trialable in a small scale,
and observability translates to successful communication of outcomes to all
relevant stakeholders. The authors also pointed out the distinction between
individuals and organizations as highly important in the health care setting.
Individuals may be innovative in one or many domains, thus making them more
likely to adopt an innovation in their health care role, but they can also be
resistant when confronted with barriers. On the other hand, organizations are
motivated by gains and resistance on the organizational level may become evident
when the implementation of an innovation is misinterpreted to coincide with
individual or group loss of power or status. The authors concluded that the various

31
stakeholders in health care form a complex network, and a wide array of different
professions needs to collaborate to ensure widespread use of an innovation. They
also emphasized that formal and informal partnerships are often needed and that
champions or “celebrity hospitals” are influential in innovation adoption and
diffusion.
Methodology
A broad review of the selected articles was conducted. The methods used
can be categorized into two main groups: systematic reviews, cross-sectional
studies, and surveys.
Systematic Reviews
In systematic reviews, authors collect and summarize previously published
studies and present it in a concise format. Even though there is no clear definition
of what constitutes a systematic review, the main characteristics are typically (a)
clear objectives with specific methodology that can be reproduced by others; (b)
an exploration of existing literature including methodology to attempt to find all
possible studies fitting the eligibility criteria; (c) validity assessment of the studies
included, for example for bias etc; and (d) a presentation of the results as a
synthesis (Moher et al., 2015). The use of systematic reviews is increasingly
common, and the quality of these reviews is improving through reporting
standardization, especially after the adoption of the Preferred Reporting Items for
Systematic reviews and Meta-Analyses for Protocols (PRISMA-P). Strengths of
systematic reviews include more precise estimates of effects than those derived

32
from individual studies and a cohesive approach to the research problem. The
main limitations are possible erroneous conclusions if all studies were not
identified. For example, Parston et al. (2015) did a systematic review of
successful innovations in health care with a significant impact on public health
and assessed the factors affecting rapid adoption. In another example, M. Jacobs
et al. (2017) conducted a literature review on the frequency of output evaluation
of innovations in RO. Output was defined as survival, toxicity, safety, service,
efficiency or cost-effectiveness. The authors looked for publications in three
ways: innovations in general health care, radiotherapy-specific innovations, i.e.,
organizational innovations and general implementation of innovations, and
innovations per tumor group/radiotherapy technique. Smith et al. (2017) did a
review of the current appropriateness of the use of advanced technologies for
radiation therapy and surgery in oncology. They focused their study on the
definition of the value of innovation implementation from multiple stakeholders
and how scientific evidence enters the marketplace of radiation oncology. The
authors specifically studied the adoption rate of two distinct innovative
techniques, IMRT in the 1990s and early 2000s and proton therapy in the 2000s.
Some of the articles cited in these systematic reviews are not explicitly mentioned
in this section, yet will be used in the synthesis section below.
Cross-Sectional Studies
Cross-sectional studies are a type of observational study that analyzes data
from a population or population sample at a specific point in time and draws

33
conclusions on the state of affairs at that moment in time. Strengths of this type of
study include a relatively low cost, rapid completion, and relative ease to achieve
large sample sizes. Limitations of cross-sectional studies are the inability to
determine causation and follow through to develop changes in the observed
patterns (Cresswell, 2018). For example, Jacobs et al. (2016) studied the degree
of innovation routinely implemented in the Netherlands by doing a descriptive
cross-sectional study. The authors used semi-structured interviews to collect
information on product innovation (number of introductions of new or
significantly improved treatments, number of new positioning devices, percent of
patients on phase I-II randomized trials, percent of patients in phase III trials),
technological innovation (frequency of implementation of new medical devices,
number of products purchased), market innovation (percentage of patients from
outside the market area, percent of referring hospitals) and organizational
innovation (new practices for organizing procedures, new methods for organizing
work responsibilities, new methods for organizing external relationships with
organizations or public institutions). Pfister et al. (2015) used Surveillance,
Epidemiology, and End Results (SEER) Medicare data to study risk-adjusted
mortality by cancer category in the Medicare population and investigated the
difference in outcomes based on university affiliation status. Pollack, Soulos, and
Gross (2015) studied peer exposure the adoption of a new cancer treatment
modality (breast brachytherapy) by using SEER data and correlated the exposure
of early brachytherapy adopted among non-early adopters by investigating their

34
shared patients. Nardi et al. (2016) did a cross-sectional analysis of five-year
survival between specialty and non-specialty cancer hospitals. Keown et al.
(2014) did a two-phase qualitative and quantitative cross-sectional study in eight
countries (Australia, Brazil, England, India, Qatar, South Africa, and the United
States) and compared cultural factors enabling health care innovation.
Surveys
While there is no research done on validating web-based surveys
specifically on MPs, Dykema, Jones, Piché, and Stevenson (2013) analyzed the
use of web-based surveys in clinicians and other health care providers and
concluded to achieve good response rate, high incentives are needed. The authors
summarize their findings to equate web-based surveys to traditional ones,
assuming a rigorous methodology and clarity in result reporting.
Literature Review Related to Key Concepts and/or Variables
Results of the literature review were thematically synthesized. Diffusion
of innovations in science and health care in its entirety is presented. Subsequently,
RO-specific implementations are assessed. Each of the following categories is
then presented as separate entities: effects on value, quality and outcomes, social
impact and predictive parameters.
Diffusion of Innovation in Science
Innovation and science have a tight-knit relationship. The terms science,
technology, and innovation are frequently used interchangeably. For example, the
United Nations Educational, Scientific and Cultural Organization (UNESCO) has

35
an entire program devoted to science, technology, and innovation, as means for
economic development and social progress (UNESCO, 2018). In the classic linear
models discussed by Eizagirre, Rodríguez, and Ibarra (2017), there is an
expectation that funding science will lead to innovation, through technological
advancements. However, this narrow approach fails to include socio-economic
context and the role of government in allowing deviation from traditional models
so mutually responsive co-responsibility can emerge between social actors.
Eizagirre et al.(2017) concluded that the relationship between science and
innovation is converging to inertia and a new paradigm is needed. The blurring of
the lines between neoliberalism and economization in the United States is
blatantly apparent when reviewing the accessibility of innovative services in
health care (Berman, 2014).
Diffusion of Innovation in Health Care in General
Over the past twenty years, there has been an exponential increase in
innovative policies, products, and practices aiming to increase life expectancy,
quality of life, effectiveness of treatment, efficiency of treatment, and equity of
delivery (Frenk, 2013). How innovations are actualized to improve public health
is often referred to as translational research. The time lag between an introduction
of an innovation and its diffuse clinical practice was estimated to be on average
17 years, however the way this time lag is measured varies depending on content
and exact research questions (Morris et al., 2011). It is logical to attempt to
shorten this time so the benefits can be maximized; in fact there is an extensive

36
body of literature on the individual and organizational characteristics that promote
acceptance and proliferation of innovation in health care (Parston et al., 2015).
Different countries are adopting different strategies to do so. Darzi and Parston
(2013) studied the local context of spreading innovations for eight different
countries and found substantial differences in cultural dynamics. In the United
States, the authors found that standards and protocols along with incentives and
rewards were the most important enabling factors for innovation, followed by
funding for research development and diffusion, communications channels across
and beyond health care, transparency of findings and data demonstrating success
and informatics. Vision and strategy, along with specific resources to identify and
promote innovation were ranked as the least important parameter for the diffusion
of innovation among expert users on the panel (Darzi & Parston, 2013).
The need for innovation in health care is broadly accepted not to be
sufficient (Harris, Bhatti, Prime, del Castillo, & Parston, 2018; S. R. Jacobs et al.,
2015). There is general agreement that innovation implementation improves
patient outcomes (Daniels & Capouya, 2017; Parston et al., 2015). There are
numerous examples of adverse patient outcomes due to ineffective
implementation of innovation in the health care setting (Reinhardt et al., 2015).
The majority of criticism against innovation is related to high costs; innovation is
often described as being too costly, as research and development alone cost
billions. These simplistic approaches often underestimate the complexity of cost-
benefit and the lower downstream costs of improved health at the individual and

37
societal level (Dzau, Asch, Hannaford, Aggarwal, & Pugh, 2017). There needs to
be a distinction, however, with low-cost yet proven approaches, especially at low
resource settings; high-cost innovative approaches are only beneficial if they
outperform their pre-existing solutions and are affordable enough to lead to
improved population health. Innovations need to sustainably show benefits to be
meaningful (Dzau et al., 2017).
The health care setting provides an excellent field to emphasize the
difference of the different levels that innovation can take place in. In their seminal
work on health care diffusion of innovation, Greenhalgh, Robert, Macfarlane,
Bate, and Kyriakidou (2004) make a health care industry-specific distinction on
the adoption by individuals and adoption by organizations. Organizational
innovativeness is affected by the administrative intensity, centralization,
complexity, internal and external communications, formalization, functional
differentiation, managerial attributes toward change, managerial tenure,
professionalism, slack resources, specialization, technical capacity, and vertical
differentiation. The individual is influenced by general antecedents (tolerance of
ambiguity, intellectual ability, motivation, values, and learning style) and context-
specific psychological antecedents (values, goals, specific skills, etc.). The
majority of publications focus on the science of diffusion, and few on the art of
change (Pedersen, 2015). There are also significant differences in how innovation
is implemented in low-resource settings (Harris et al., 2018).

38
Diffusion of Innovation in RO
RO prides itself as a high technology field. Linear accelerators, atomic
particles, and algorithms work harmoniously to cure cancer. There is currently
extensive usage of many advanced cutting-edge technologies: (a) computational
advances using graphics processor units (GPUs), cloud-based methods, and
parallel processing have improved calculation speed and are being used for
automated knowledge-based treatment planning; (b) high performance imaging
systems such as positron emission tomography (PET) allow tumor identification
and radiotherapy response measurement, and onboard magnetic resonance
imaging (MRgRT) improves real-time monitoring; (c) heavy particle treatments
better spare healthy tissues, especially in pediatric populations. However, the field
has not universally accepted these innovations (Chetty et al., 2015) and little is
known about the factors that may influence groups and individuals (Pollack et al.,
2015). This may be partly affected by the fact that few publications include the
term "innovation," while in reality, they are actually describing an innovative
technique (M. Jacobs et al., 2017).
M. Jacobs et al. (2015) applied the Delphi method to determine indicators
for innovation in RO and derived 13 indicators in four categories:
Product innovation: number of introductions of new or significantly
improved treatments, number of new positioning devices for patient
treatments, number of approved patents, percentage of patients in

39
phase III randomized trials approved by an IRB, percentage of patients
in phase I-II trials approved by an Institutional Review Board (IRB)
Technological innovation: frequency of implementation of new
medical devices, number of products for which royalties have been
obtained or which have been sold to the industry, number of regulatory
agency approved marked products that have been produced by the
department (for example regulated by the Food and Drug
Administration (FDA), or the Conformité Européenne (CE))
Market Innovation: percentage of patients from outside the market
area, number and percentage of new general hospitals that refer to the
desired patient population.
Organizational innovation, new practices and for organizing
procedures, new methods of organizing work responsibilities and
decision making, new methods of organizing external relationships
with other organizations or public institutions
The authors suggest that these indicators are most useful when measured
in the past three calendar years. These indicators are useful in an attempt to study
innovation in RO. Yet, there is currently no study that systematically quantified
the diffusion of innovation in RO in the United States. Innovation implementation
has been more successfully quantified in the Netherlands with a small number of
centers. Jacobs et al. (2016) studied 15 Dutch RO cancer centers (75% of the total
in the Netherlands) and found that they implement on average12 innovations per

40
year (range 5-25). The authors will attempt to repeat at three-year increments. The
average number is sufficiently large and the authors concluded that Dutch
radiotherapy centers are highly accepting of innovation. The wide range,
however, suggests a non-homogenous distribution, which the authors did not find
to be attributed to academic status. The authors concluded that systematic
collaboration between centers and a national registry would be beneficial to
improving innovation implementation even further.
Value of Innovation
The definition of value in health care is not very clear. As mentioned
before, some of these innovations are extremely expensive and frequently out of
reach for standalone community hospitals. Even though one can argue that the
investment in innovative technologies translated to increased income for the
providers and hospitals and to increased quality-adjusted life-years, the math is
not straightforward in RO. In MO, the development of new pharmaceuticals may
increase the cost of treatment for new, promising chemotherapy agents directly
improves outcomes (Roubou & Alexopoulou, 2015). In RO, innovations need
long-term investments to sustain the appropriate use of the technology in the form
of upgrades, service contracts, staff education, etc (Smith et al., 2017). There is
also a broad discussion of reimbursement for innovative techniques. If the
innovative technique has an associated financial motive, then the decision to
implement it may be spurious at best. The higher reimbursement rates for IMRT
discussed previously were certainly a contributing factor to its fast and successful

41
diffusion across the United States. Conversely, some of the innovative techniques
available reduce the number of total treatments and the overall provider and
hospital reimbursement. A common example is the use of hypo-fractionated
versus conventional whole breast irradiation in the United States: despite
supportive 10-year data from the United Kingdom, only 11% of eligible patients
received this shorter and less costly regiment in 2008 and 35% in 2013 (Bekelman
et al., 2014). In the absence of financial incentives, providers are less likely to
adopt innovative treatments that may improve outcomes but reduce their direct
financial benefit. In health care in general, value can mean societal value, such as
lost wages, lost productivity, and willingness to pay, care value, such as disease
control, quality of life and theoretical long-term benefits, or system value, such as
incremental costs, budget impact and affordability (Smith et al., 2017). All these
three constitute a cost-effective ratio to consider an innovative technique to be of
better value than the established technique, and there is little agreement on the
calculation of this ratio. Usage of lower cost but better techniques does have
successful examples from DR. The Joint Task Force on Adult Radiation
Protection was created by the collaboration between the American College of
Radiology and the Radiological Society of North America with the purpose
addressing the public’s concern about exposure to ionizing radiation from medical
imaging. The Joint Task Force collaborated with the American Association of
Physicists in Medicine and the American Society of Radiologic Technologists to
develop standards and launch an extensive awareness campaign under the slogan

42
“Image Wisely” for adults and “Image Gently” for pediatric patients (American
College of Radiology, 2011). These efforts are focused on optimizing existing
techniques to limit unnecessary exposure, and often inadvertently highlight the
limitations of older equipment. Approaches such as this provide a clear statement
to the market and to practitioners that they need better and different innovations.
Effects on quality and outcomes. In the field of RO, innovative
techniques are often implemented based on the “as low as (is) reasonably
achievable” principle (ALARA). This principle means “making every reasonable
effort to maintain exposures to ionizing radiation as far below the dose limits as
practical, consistent with the purpose for which the licensed activity is
undertaken, taking into account the state of technology, the economics of
improvements in relation to state of technology, the economics of improvements
in relation to benefits to the public health and safety, and other societal and
socioeconomic considerations, and in relation to utilization of nuclear energy and
licensed materials in the public interest” (Nuclear Regulatory Commission, 2018).
In RO, innovations are frequently implemented using this principle, in the
absence of clinical trials, and there is broad agreement that this improves quality
and outcomes (M. Jacobs et al., 2017). While clinical trials are typically the gold
standard for evidence-based approaches (Daniels & Capouya, 2017), the
implementation of innovative techniques using ALARA is extensive in RO
(Chen, 2014). Since there are no clinical trials to drive nationwide
recommendations, users can choose their own methods on how to treat patients,

43
within the broad standards described by the National Comprehensive Cancer
Network (National Comprehensive Cancer Network, n.d.). This leads to
significant differences in outcomes for different populations and leads to the
conclusion that quality of cancer care in the United States is inconsistent, with
patients treated at specialty cancer hospitals having an adjusted 10% lower
mortality at one year than patients treated at community hospitals (Pfister et al.,
2015). This inequality to access to appropriate cancer care may not be solely due
to innovations, but it is certainly a parameter (Nardi et al., 2016). Additionally,
there is little innovation implementation in using big data in RO. Since the advent
of electronic medical records (EMR), there has been little or no standardization of
specific field entry. The most basic example is the radiation prescription: after ten
years of discussion, there is barely a draft in progress (personal communication,
RO-SSI group, July 16, 2019). This makes data extraction and comparison
extremely difficult and often meaningless. Data elements such as survival,
recurrence, diagnosis and staging, provider-reported toxicities, dosimetric data
from delivered plans, and use of innovative technologies (such as breath-hold,
image-guided radiation therapy, immobilization devices) are largely missing as
elements in most EMRs. Extracting this data automatically would lead to self-
evaluation and scoring relative to national standards, thus improving the adoption
of standards (Mayo et al., 2016).
Social impact. Different cancer care treatments especially in
hepatobiliary, lung, pancreas, gastric, breast, cervical, oral, and colorectal cancer,

44
where patients five-year survival is higher by 20-30% for patients treated at
comprehensive cancer centers designated by the National Cancer Institute
(NCICCC) (Nardi et al., 2016). These NCICCCs are disproportionally located in
the eastern United States and major cities across the country (National Cancer
Institute, 2018b). The average American living in a rural area has to travel an hour
to reach specialized oncology care, and an hour and a half to reach a university
hospital (Charlton et al., 2015). Many patients live so far away from an NCICCC,
they simply do not have the option to seek treatment there. Additionally, many
health care plans do not cover services at university hospitals or NCICCCs at all
(Nardi et al., 2016). This translates to the majority of Americans not having
access to centers that provide better cancer outcomes, either because of
geographical limitations or because their insurance does not cover treatment at
institutions with proven better outcomes. This is one of the many challenges in
modern America, especially in rural areas. One of the ten essential services of
public health is to “evaluate effectiveness, accessibility, and quality of personal
and population-based health services” (Centers for Disease Control and
Prevention, 2017). The possible lack of diffusion of innovation in RO is a factor
that is often overlooked in improving population health. Providing RO care of the
highest quality to all patients by improving the utilization of innovative FDA-
approved techniques wound contribute to the improvement of accessibility and
quality of RO services across the United States and subsequently improve cancer
outcomes. This would be a contribution to positive social change.

45
Organizational Predictive Parameters
Academic affiliation status has been shown to have a positive main effect
on innovation and accessibility of services, possibly through slack staffing
resources and increased financial resources (Wisdom et al., 2014). Urbanicity has
been shown to have a positive effect on innovation and accessibility of services,
possibly through competition (Angst, Agarwal, Sambamurthy, & Kelley, 2010;
Charlton et al., 2015). Employment type details and type of practice have an
unclear relationship with innovation. Organizational structure and climate have
been shown to influence innovation adoption, possibly through fecund
management tiers (Angst et al., 2010; Wisdom et al., 2014); the number of
physicists and reporting structure will be used to assess the organizational
structure and climate for MPs.
Individual Predictive Parameters
Gender has a complicated relationship with innovation and there are
conflicting results in the literature (Lee, 2016). Recent research focuses on
entrepreneurship and gender ratios on the executive level and its relationship to
organizational innovation and success (Belghiti-Mahut, Lafont, & Yousfi, 2016).
The possible influence of gender in MPs practicing in RO is not certain, and it
will thus be interesting to include this parameter in the analysis. On the contrary,
the effects of education and age are well studied. Age typically has a negative
main effect on innovation adoption (younger people are more likely to adopt
innovations) and education typically has a positive main effect on innovation

46
adoption (people with higher education levels are more likely to adopt
innovations) (Arts, Frambach, & Bijmolt, 2011). Social status typically has a
positive main effect on innovation adoption (people with higher status are more
likely to adopt innovations) (Rogers, 2003); affiliation with academic institutions
will be used to assess the social status in MPs. Interpersonal channels typically
have a positive main effect on innovation implementation (people with more
intrapersonal channels are more likely to adopt innovations) (Rogers, 2003); the
number attendances in national meetings will be used to assess interpersonal
channels in MPs. Organizational structure and climate have been shown to
influence innovation adoption (people in larger, well-organized groups are more
likely to adopt innovation) (Wisdom et al., 2014); the number of physicists and
reporting structure will be used to assess the organizational structure and climate
for MPs. Motivation and appreciation are two individual characteristics that are
frequently used to assess the position of the individual in the stages previously
described by Rogers (2003) (Wisdom et al., 2014); the sense of appreciation and
motivation will be directly assessed in the study participants as context-specific
psychological antecedents. Appreciation and motivation typically have a positive
main effect on innovation adoption, as they may increase the individual’s
tolerance of risk (people who feel appreciated and motivated are more likely to
adopt innovations). Similarly, opinion leadership typically has a positive main
effect on innovation adoption (people who consider themselves opinion leaders

47
are more likely to adopt innovations) (Arts et al., 2011); volunteering in AAPM
committees will be used to assess the opinion leadership of MPs.
Summary and Conclusions
Innovation implementation is an area that needs improvement in science,
health care in general and in RO specifically. The diffusion of innovation
theoretical framework is one of the oldest social science theories, and it is well
studied in health care, thus grounding the literature review. In this study, the
results of the literature review were thematically synthesized to diffusion of
innovations in health care in general, diffusion of specific innovations in RO,
effects on value, effects on quality and outcomes, social impact, organizational
and personal predictive parameters.
The state of diffusion of innovation in RO in the United States is currently
not measured, but it is suspected to follow the low rates experienced in other
health care fields. There are many underutilized innovations in RO that can
enhance patient and staff safety and improve patient outcomes simultaneously.
Developing a tool to measure innovation will be the first step in developing a
predictive model to improving its diffusion. There is currently no systematic
quantification of diffusion of innovation in RO in the United States, and no
existing secondary dataset that can be used to extract this information.
Understanding the individual and organizational real and perceived barriers to
implementing innovations would create the framework to overcome them. If
something is not measured, there is no opportunity to study it and further improve

48
it. There needs to be enhanced understanding of how innovative techniques are
adopted in RO specifically and assess any disparities in technology
implementation in RO in the United States.
To this end, the following chapter describes the methods used to
systematically collect this data. A custom-designed online survey was created to
conduct a quantitative cross-sectional analysis of how MPs practice and utilize
FDA-approved innovative techniques in the academic vs. community setting and
rural vs. urban geographic locations. This provided the framework to develop a
predictive model assessing possible barriers at the individual (MPs) and
organizational (RO clinic) level, based on the previously discussed constructs.
Details of the survey design, sampling procedures, power analysis, data analysis,
threats to validity, and ethical procedures will be presented in the next chapter.

49
Chapter 3: Research Method
Introduction
As stated in Chapter 1, the purpose of this study was to investigate the
accessibility of innovative services in RO in the United States and assess possible
diffusion patterns using a quantitative cross-sectional survey. Surveying MPs to
measure the diffusion of innovation in RO is in alignment with the ninth essential
function of public health services to “evaluate effectiveness, accessibility, and
quality of personal and population-based health services” (Centers for Disease
Control and Prevention, 2017). As there are currently no indicators or instrument
for measuring the accessibility of innovative services in RO in the United States,
according to the literature review, this study quantified this issue and attempted to
explain the barriers to adoption of innovative technologies in RO. In this chapter,
the focus is on explaining the research design and rationale and the methodology
used. The sampling and recruitment procedures are also discussed, as are the
instrumentation and operationalization of constructs as they relate to the specific
topic. Last, the threats to validity and ethical procedures are addressed.
Research Design and Rationale
This study aimed to measure the innovation score in RO in the United
States. Innovation score is the dependent variable. For the purposes of this study,
innovation score is defined as the sum of innovation indicators on product,
technology, and organizational innovation. Product and technological innovation
were measured as the ratio of the number of innovative techniques available or

50
purchased by a department divided by the number of the innovative techniques
used clinically, weighed by partial implementation factors. Organizational
innovation was measured as the weighted average of innovations used to
reorganize procedures, work responsibilities, and decision-making.
Independent variables in this study included variables at both the
organizational and individual level. At the organizational level, independent
variables included university affiliation and urbanicity. At the personal level,
independent variables included gender, age, education, attendance of residency,
certification status, interpersonal channels, leadership structure, group size,
opinion leadership, appreciation, and motivation.
The research design selected to investigate the possible connections
between the dependent and independent variables was a quantitative cross-
sectional survey. Survey research is typically used for exploration, explanation, or
description and involves the collection of descriptive, behavioral, and attitudinal
data (Burkholder, 2015). In this study, survey research was used for explanatory
purposes by collecting descriptive and behavioral data. Innovation score is not
directly measured by any organization or vendor; thus, the only way to measure it
was to ask MP responders to describe how they use innovations in their work and
design a custom survey. Even if there were existing data on organizational
characteristics and innovation implementation, individual level characteristics
would not have been included. It was, therefore, necessary to reach out to
individual MPs and collect self-reported data.

51
The survey was conducted exclusively online. This type of design is
predominant in studies by health professionals, especially doctoral students
(Rudestam & Newton, 2014). Web survey research has been shown to have lower
costs, shorter length of time for field research, more flexible questionnaire design,
higher percentage of questions answered completely and accurately, higher ability
to administer complex instruments, shorter date processing time, lower error due
to manual data entry, faster survey deployment, and a larger amount of available
para-data (Dykema, Jones, Piché, & Stevenson, 2013). Potential disadvantages of
Web survey designs include required access to Internet and email, the requirement
of high computer literacy, increased likelihood of incomplete and erroneous
contact information, lower response rates, slightly lower demographic
representativeness, and decreased ability to administer incentives effectively
(Dykema et al., 2013). For the purposes of this study, a web survey was selected
because email communication is extensively used by and the preferred method of
communication of MPs (American Association of Physicists in Medicine, 2017).
Coincidentally, the use of a web survey aligned with the time and resource
limitations of the study.
Methodology
Population
In 2018, the AAPM directory listed approximately 7,500 members in total,
and approximately 5,500 members are listed as active in the United States (not
student, retired, associate, or corporate members) (American Association of

52
Physicists in Medicine, 2018). Seventy-seven percent of the membership reported
being active in RO (American Association of Physicists in Medicine, 2018); thus,
there were about 4,200 eligible MPs. Unofficial surveys typically garner an
approximate 5-10% response rate and official surveys an approximate 30-35%
response rate. (American Association of Physicists in Medicine, 2017)
Considering this response rate and the estimated number of AAPM members,
approximately 200 responses were expected for this survey.
Sampling and Sampling Procedures
Primary data was collected for this study using total population
convenience sampling because the population is finite and a list was readily
available. The MedPhysUSA listserv and AAPM Blackboard were used to recruit
participants. The MedPhysUSA listserv is used extensively among MPs for
survey dissemination, exchange of ideas, and general discussion. The listserv is
hosted by Wayne University and had over 4,000 members at the time of study.
Users must subscribe, and there are volunteer moderators. Forum policies were
followed; no official permission was needed to post. The AAPM Blackboard is
hosted by the AAPM and is open to all members for exchange of ideas and
general discussion. No special permission was needed to post the survey. The
survey was also posted on LinkedIn. LinkedIn retains data on user activity, as
described in its privacy policy (“Privacy Policy, LinkedIn,” n.d.). All users agree
to this policy as a condition of using the platform. The survey was designed using

53
an online survey research platform called SurveyMonkey (SurveyMonkey, 2019).
The invitation post included brief description of the study and a link to the survey.
Based on the expected participant number, a 5% chance of a Type I error
and a 20% chance of a Type II error was reasonable. Statistical power of 80% was
a reasonable initial goal as well. The typical four-to-one weighting was a good
starting point for this study, and it will be further assessed after data collection. If
the preliminary analysis reveals disproportional response rates between the
categories of interest, these numbers may need to be altered. Type II errors, which
encompass not detecting an effect that is actually there, or a false negative
(Salazar, Crosby, & DiClemente, 2015), posed more significant social
implications than Type I errors in this study. Not detecting an underperformance
in community and rural RO centers might have led to a lack of supplemental
efforts from AAPM to boost their utilization of new techniques and continuing
population inequalities. Effect sizes are unknown since innovation in the United
States has not been previously measured. Small to medium effect size of 0.2 were
assumed. Based on these assumptions, G-Power (Faul, Erdfelder, Lang, &
Buchner, 2007) calculated that approximately 200 responses were needed.
Procedures for Recruitment, Participation, and Data Collection
Participants were contacted passively by using the forums mentioned
above. The invitation contained a brief description, incentive information, and a
link to participate. Two reminders were sent approximately 10 days apart. The
survey remained open for a total of thirty days. When participants opened the

54
link, they were taken to the introductory study page, where they were asked to
consent to participate in the study. The survey contained a total of 70 questions
and took approximately 5-10 minutes to complete (SurveyMonkey, 2018).
Participants were asked multiple demographic and practice information as
described in other sections. Participants were asked to enter an email address if
they wish to receive a $10 Amazon gift card as an incentive to participate. This is
a reasonable amount, as MP’s salaries start at $140,000 (American Association of
Physicists in Medicine, 2018). The incentive was used to encourage participation.
Dykema et al. (2013) analyzed the use of web surveys in clinicians and other
healthcare providers and concluded that to achieve good response rate, incentives
are needed to improve participation rates. Participants will exit the study after
they complete the survey. No follow-up procedures are applicable.
Instrumentation and Operationalization of Constructs
Studies attempting to define and measure innovation in RO rely on custom
survey design, as there is no centralized reporting mechanism. This was described
in Chapter 2 as discussed by M. Jacobs et al. (2015) and Jacobs et al. (2016). This
survey is an extension of the work done by these groups, who validated their
innovation indicators using the Delphi method. Briefly, this Dutch group used
consensus guidelines among RO chairpersons to define innovation in RO and
used semi-structured interviews across 15 RO centers.
Reliability and validity. Reliability was measured using inter-item
reliability and split-half method. Chronbach’s alpha of 0.7 or higher was be used

55
to assess sufficient evidence of internal reliability (Salazar, Crosby, &
DiClemente, 2015). Face validity and content validity were demonstrated by an
expert panel. The expert panel was used to assess clarity of wording, applicability
of answers, etc. Five MPs who fit the eligibility criteria were contacted in
November 2018 and asked to review the survey and identify any ambiguity in the
wording of the questions. Each expert panel participant was contacted via email
and sent a preliminary version of the survey. Feedback was requested in writing
within a week. Comments were received during a two-week period. Comment
examples included the anonymity of the survey, stratification techniques, and
length of the consent form. Additionally, comments were requested from the
AAPM Technology Assessment office and received within 2 weeks in January
2019. Four blinded field experts reviewed the survey and provided feedback on
the structure and levels of measurement. All comments were used to improve the
survey questions before deploying the study to the target population and enhance
the study’s validity, as discussed in subsequent sections. Construct validity was
demonstrated using principal component analysis (PCA) after data collection.
Operationalization of Constructs. The dependent variable in this study is
innovation score, which is defined as the sum of innovation indicators on product,
technology, and organizational innovation. Product and technological innovation
were measured as the ratio of the number of innovative techniques available or
purchased by a department divided by the number of the innovative techniques
used clinically, weighed by partial implementation factors. Organizational

56
innovation was measured as the weighted average of innovations used to re-
organize procedures, work responsibilities, and decision making. This is a
continuous variable. For example, assume that there are ten indicators for product,
technology, and organizational innovation and one of the responders has five
available for use in their clinic. Out of those five, they use the first two all the
time (100%), the third one most of the time (75%) and the last two half of the
time (50%). The innovation score for this respondent will be
(5/10)*[(100+100+75+50+50)/5] = 0.5*0.75 = 0.375.
The independent variables are described in detail in Table 1. University
affiliation was measured as a binary yes or no. Zip code text entry was converted
to categorical using the RUCA continuum (USDA, 2013), explained in Appendix
C. Gender was binary male or female. Age was measured as a continuous variable
and was recoded into categorical. Education was measured as Master’s, Doctoral
or other. Residency status was measured as a categorical variable, (yes, no, no
didn’t need). ABR status was measured as yes, yes/other, or no. Interpersonal
channels were measured as a continuous variable, using the number of meetings
attended. Organizational structure was be measured as a categorical variable as
physicist, physician, administrator. Group characteristics were measured as a
categorical variable based on the size of the group. Opinion leadership was
measured as a binary variable as yes or no. Appreciation was measured as a
continuous variable. Motivation was measured as a continuous variable. Barriers
were measured as continuous variables.

57
Table 1
Operationalization of Constructs
Question Variable
Level of
measurement RQ
Q3-57 Innovation score
(dependent variable) Continuous 1, 2 3
Q1: university affiliation University affiliation Binary 1a
Q2: location Zip code Categorical 1b
Q3-57 Barriers Continuous 3
Q58: gender Gender Categorical 2
Q59: Age Age Continuous 2
Q60: degree Degree Binary 2
Q61: residency Residency Categorical 2
Q62: ABR status ABR status Categorical 2
Q63: meeting attendance Interpersonal channels Continuous 2
Q64: reporting organizational structure Categorical 2
Q65: # of physicists Group characteristics Categorical 2
Q66: volunteering Opinion leadership Categorical 2
Q67: appreciation Appreciation Continuous 2
Q68: motivation Motivation Continuous 2
Q69: final thoughts Free text - -
Q70: gift card Free text - -
Data Analysis Plan
After completing data collection, SPSS version 25 was used for statistical
analysis. Data were screened for duplicates. Missing entries were reviewed for
randomness, and data were removed pairwise when applicable. The RQs and
hypotheses were as follows:
RQ 1: What are the differences in accessibility to innovation in RO based on
location and type of practice in the United States?

58
RQ 2: What are the statistically significant factors (demographics, practice details,
context-specific psychological antecedents) that predict the accessibility to
innovation in the RO clinic?
RQ 3: What are the statistically significant barriers that MPs practicing in RO in
the United States face in implementing innovations?
Hypothesis 1a
H1a0: There is no statistically significant difference in accessibility to
innovation in RO between university and non-university hospitals.
H1a1: There is a statistically significant difference in accessibility to
innovation in RO between university and non-university hospitals.
Dependent variable: innovation score (continuous).
Independent variable: university affiliation (categorical, two levels: has
university affiliation, does not have university affiliation).
Hypothesis 1b
H1b0: There is no statistically significant difference in the accessibility to
innovation in RO between metropolitan and non-metropolitan hospitals.
H1b1: There is a statistically significant difference in accessibility to
innovation in RO between metropolitan and non-metropolitan hospitals.
Dependent variable: innovation score (continuous).
Independent variable: urbanicity (categorical, metropolitan and non-
metropolitan).

59
Hypothesis 2
H20: There are no statistically significant factors predicting innovation
score.
H21: There are statistically significant factors predicting innovation score.
Dependent variable: innovation score (continuous).
Independent variables: reporting structure, size of physics group, age,
gender, DABR status, residency status, meeting attendance, education
level, leadership,(categorical) appreciation, and motivation (continuous).
Hypothesis 3
H30: There are no statistically significant barriers affecting innovation
score.
H31: There are statistically significant barriers affecting innovation score.
Dependent variable: innovation score (continuous).
Independent variables: barriers (continuous).
Analysis plan. For RQ 1 the purpose is to compare groups, thus t-test and
ANOVA were used (Frankfort-Nachmias & Leon-Guerrero, 2015). T-test was
used to compare innovation score for type of hospital variable and ANOVA was
used to compare innovation between the RUCA urbanicity continuum. The t and
F values and p-value were reported, along with means and standard deviations for
all groups. Alternative non-parametric tests, such as the Mann-Whitney U and
Kruskal-Wallis H tests, would have been selected if the dataset was found to have
a significant deviation from normality. If homogeneity of variance was met,

60
Tukey's honestly significant difference (HSD) post hoc test was used to assess
which specific groups differed. If the data did not meet the homogeneity of
variances assumption, the Games Howell post hoc test would have been
considered.
For research question 2, multiple linear regression was initially planned to
be used if the assumptions of linearity were met. The dependent variable was
innovation score. This is a continuous variable. Independent variables in the
model were respondents’ age, gender, education level, ABR status, residency
status, interpersonal channels, appreciation level, motivation level, opinion
leadership, practice organizational structure, and group characteristics. Alternative
non-parametric tests were selected because the data did not meet normality
criteria. To do so, the dependent variable (innovation score) was recoded to be
binary categorical (below median, above median) and binomial logistic regression
was used instead.
For research question 3, correlation testing was used. The dependent
variable was innovation utilization score. The independent variables are the
individual barriers (lack of evidence, complexity, lack of time or staffing, lack of
training or support, lack of interest, lack of interoperability, and lack of
reimbursement. Pearson’s correlation was selected if the relationship between the
dependent and independent variable is linear. Spearman correlation was selected
if the data did not meet normality criteria.

61
Threats to Validity
Threats to External Validity
This study will reach the entire MPs population in the United States, thus
threats to external validity due to sampling are limited (Cresswell, 2018). There
is, however, the problem of volunteer bias, as participants who volunteer to be in
a study about innovation may inherently be more innovative. The respondents
may not be representative of the general population in regards to innovation
practice or other characteristics. Additionally, there is inherent generalization
across constructs on how the constructs apply to MPs specifically. For example,
opinion leadership as a construct will be measured using volunteering in the
AAPM. While participation in professional association leadership is a measure of
opinion leadership in other disciplines (B. L. Jacobs et al., 2017), there is an
inherent assumption that this connection transfers to MPs as well. This
generalization across constructs may lead to extraneous or confounding variables
in MPs.
Threats to Internal Validity
Extraneous effects may pose a threat to the internal validity of this study,
as there may be excluded extraneous variables that were elusive during the
literature review. This threat was minimized by the use of an expert panel who
reviewed the survey before implementation. Additionally, there may be personal
biases, which should be minimal due to the quantitative nature of the study.
Participant reactivity may also be present in the study, as participants may

62
respond as being more innovative than they really are, suspecting that this is the
desired behavior. This may affect the measurement of the dependent variable This
is unlikely to have significant effects on an online professional survey, as this is
most often observed in laboratory settings. These possible effects will be
minimized as much as possible with the use of the appropriate multivariable
analysis (Frankfort-Nachmias & Leon-Guerrero, 2015).
Ethical Procedures
Ethical considerations for the participants. Research participants have a
moral obligation to answer truthfully. There are many surveys performed through
the AAPM, including salary surveys for workforce forecasting, and
confidentiality is not really a concern among members. The participant obligation
will be emphasized at the beginning of the study, where the study's scope and
rationale will be explained, in addition to the time commitment expected by the
participants. Participants will be asked to acknowledge the expectations of their
participation. This acknowledgment will serve as consent and as a “contract”
between the participant and the researcher (Rudestam & Newton, 2014).
Participants who are not MPs practicing in RO in the United States, yet
participated for various reasons, would have violated the ethics of the consent.
Various methods were used to positively reinforce truthful answers. Using
a continuous, dependent-response scale (0-100 values) instead of a discrete,
Likert-type scale for partial implementation is expected to have participants

63
answer more truthfully, versus a yes or no answer that may not be indicative of
how exactly they are using these techniques.
Ethical considerations for the researcher. The survey poses minimal
risk to the participants, as the questions do not fall into the “traditional” sensitive
information areas. Information can be perceived as sensitive when it involves
cultural taboos, the threat of disclosure, or social desirability. What information is
too private, or taboo, is extremely subjective and highly dependent on the culture
(Epstein, Santo, & Guillemin, 2015). Participants were asked questions about how
they perform their daily work duties, and none of the questions is of sensitive
nature. The survey questions can, however, be seen as a surrogate to professional
performance, and thus affect the respondent’s view of performance and self-
worth. Additionally, some of the questions will be about feelings of appreciation
in the workplace. This may affect participants, as they typically may not have to
think about something like that (Rudestam & Newton, 2014). This effect may be
positive or negative, depending on the person and the situation. Possibility feeling
uncomfortable was thus included in the study consent.
Concerns over privacy will be handled using the anonymity features of the
survey provider. The custom link will be provided along with the introductory
text for the email. Email addresses will not be tracked. Additionally, concerns
over Internet Protocol address (IP) tracking will be addressed by turning the
feature off in the survey provider.

64
Institutional approval to conduct research. The Walden University
Institutional Review Board (IRB) approved this study on April 24, 2019 (approval
number 04-24-19-0603259, expiring April 23rd, 2020).
Summary
In this chapter, a detailed discussion of the research design and rationale
as a total population convenience sampling cross-sectional survey was presented.
The methodology, population, sampling procedures, instrumentation, and
operationalization of constructs, data analysis plan were discussed. Possible
threats to validity were also explored. The results of the study will be presented in
Chapter 4.

65
Chapter 4: Results
Introduction
The purpose of this research study was to examine the diffusion of
innovation in RO in the United States. To assess diffusion, a variety of statistical
tests was used to compare innovation score with organizational and personal
characteristics. A summary of the results is presented in this chapter. The
following RQs were answered:
RQ 1: What are the differences in accessibility to innovation in RO based on
location and type of practice in the United States?
RQ 2: What are the statistically significant factors (demographics, practice details,
context-specific psychological antecedents) that predict the accessibility to
innovation in the RO clinic?
RQ 3: What are the statistically significant barriers that MPs practicing in RO in
the United States face in implementing innovations?
Data Collection
The survey was posted on Saturday, April 27, 2019. The invitation is
listed in Appendix B. During the first two weeks of the survey, 136 responses
were collected. The first reminder was sent on Saturday, May 11, 2019, and the
last reminder was sent on Wednesday, May 22, 2019. The survey closed on
Saturday, June 1, 2019, at 11:50 pm. At the survey closure, 265 responses were
collected. Twenty-five responses contained no answers at all. Thus, the final

66
sample size was 240. Incomplete data entries were excluded pairwise when
applicable. The analysis was conducted using SPSS 25.
Descriptive Statistics
Independent variables were recoded as needed, taking into account the
number of responses received. ZIP codes entered in the survey were converted to
county, and the Rural-Urban Continuum Codes (Appendix C) were used to
categorize locations as metropolitan and nonmetropolitan (USDA, 2013), as
shown in Table 2. Most responses were received from metropolitan areas.
University affiliation is also listed in Table 2; the sample contained approximately
equal responses between university and non university facilities. Sample
demographics for gender, education and age are shown in Table 3. Descriptive
statistics for respondent appreciation and motivation are shown in Table 4.
Sample professional characteristics for residency, DABR status, number of
meetings in the past 10 years, reporting, number of physicists and volunteering
are shown in Table 5. Principal component analysis was found to not a suitable
test, as the overall Kaiser-Meyer-Olkin measure ranged from 0.588 to 0.634
depending on the factors entered in the model.

67
Table 2
MPs Characteristics for RO center University Affiliation and Urbanicity
Characteristic N f %
University Affiliation 240
Yes 111 46.3
No 129 53.8
Urbanicity 220
RUCA Cat 1 138 62.7
RUCA Cat 2 50 22.7
RUCA Cat 3 17 7.7
RUCA Cat 4 4 1.8
RUCA Cat 5 4 1.8
RUCA Cat 6 4 1.8
RUCA Cat 7 3 1.4
Urbanicity Binary 1 220
RUCA Cat 1 138 62.7
RUCA Cat 2-9 82 37.3
Urbanicity Binary 2 220
RUCA Categories 1-3 205 93.2
RUCA Categories 4-9 15 6.8

68
Table 3
MPs Demographics for RO
Characteristic N f %
Gender 188
Male 155 82.4
Female 33 17.6
Education 190
Master’s 118 62.1
Doctoral 72 37.9
Age distribution 183
< = 30 23 12.6
31-40 70 38.3
41-50 36 19.7
51-60 30 16.4
> 60 24 13.1
Table 4
Descriptive Statistics for RO Appreciation and Motivation in MPs
N M SD
Appreciation 190 69.16 26.728
Motivation 190 76.35 23.463

69
Table 5
MPs Professional Characteristics
Characteristic N f %
Residency 185
Yes
77 41.6
No
108 58.4
DABR status 188
DABR 150 79.8
not DABR/other 38 20.2
Number of meetings in the past 10 years 179
0-5 104 58.1
6-9 42 23.5
> = 10 33 18.4
Reporting 189
Another physicist 114 60.3
Physician 22 11.6
Administrator 37 19.6
VP/CEO 16 8.5
Number of physicists 191
1-3 98 51.3
≥ 4 93 48.7
Volunteer 185
Yes 72 38.9
No 113 61.1

70
Dependent variable coding. The dependent variable, innovation score,
was measured using 20 unique indicators in five categories: patient positioning,
patient treatment, treatment planning, quality assurance, and workflow, as shown
in Appendix D. Participants answers were entered using a slider with scale 0-100.
For values entered as 0 or 1 on the slider, it was assumed that the respondents
meant to not move the slider at all and that the type of innovation was not
available. For values entered as 2 to 100 on the sliding scale, it was assumed that
the respondents had the technology available to them. This categorized each
respondent as having or not having the innovation. The innovation indicators were
summed to calculate the innovation score for each category and the total
innovation score for each respondent. This provided a measure for the diffusion of
available innovative techniques and will be subsequently referred to as innovation
score. The distribution is shown in Figure 1, and it appears to be normally
distributed.
Further, the exact number on the scale of individual responses was used to
assess how respondents actually used the innovations available to them. This will
be subsequently referred to as innovation utilization score, and it is distinctly
different from the previously defined innovation score. A similar method
described for innovation score was used for the innovation utilization score. The
mean of the responses in each of the indicators in each category was used to
calculate the innovation utilization score in each category separately. The
innovation utilization score was calculated by adding the innovation utilization

71
score in the five categories. The distribution is shown in Figure 2, and it appears
to be normally distributed.
The Shapiro-Wilk test for normality was performed for innovation score
and innovation utilization score, using university affiliation and urbanicity as
factors. The results of the Shapiro-Wilk test were not statistically significant for
the innovation score (p = 0.611) and for the innovation utilization score (p =
0.699). Thus, the data were normally distributed. The Q-Q plots were also normal.
The 20 parameters used to measure innovation were assessed for the
reliability of the construct. The scale had a high level of internal consistency, as
determined by a Cronbach's alpha of 0.963.
Figure 1. Distribution of RO innovation score.
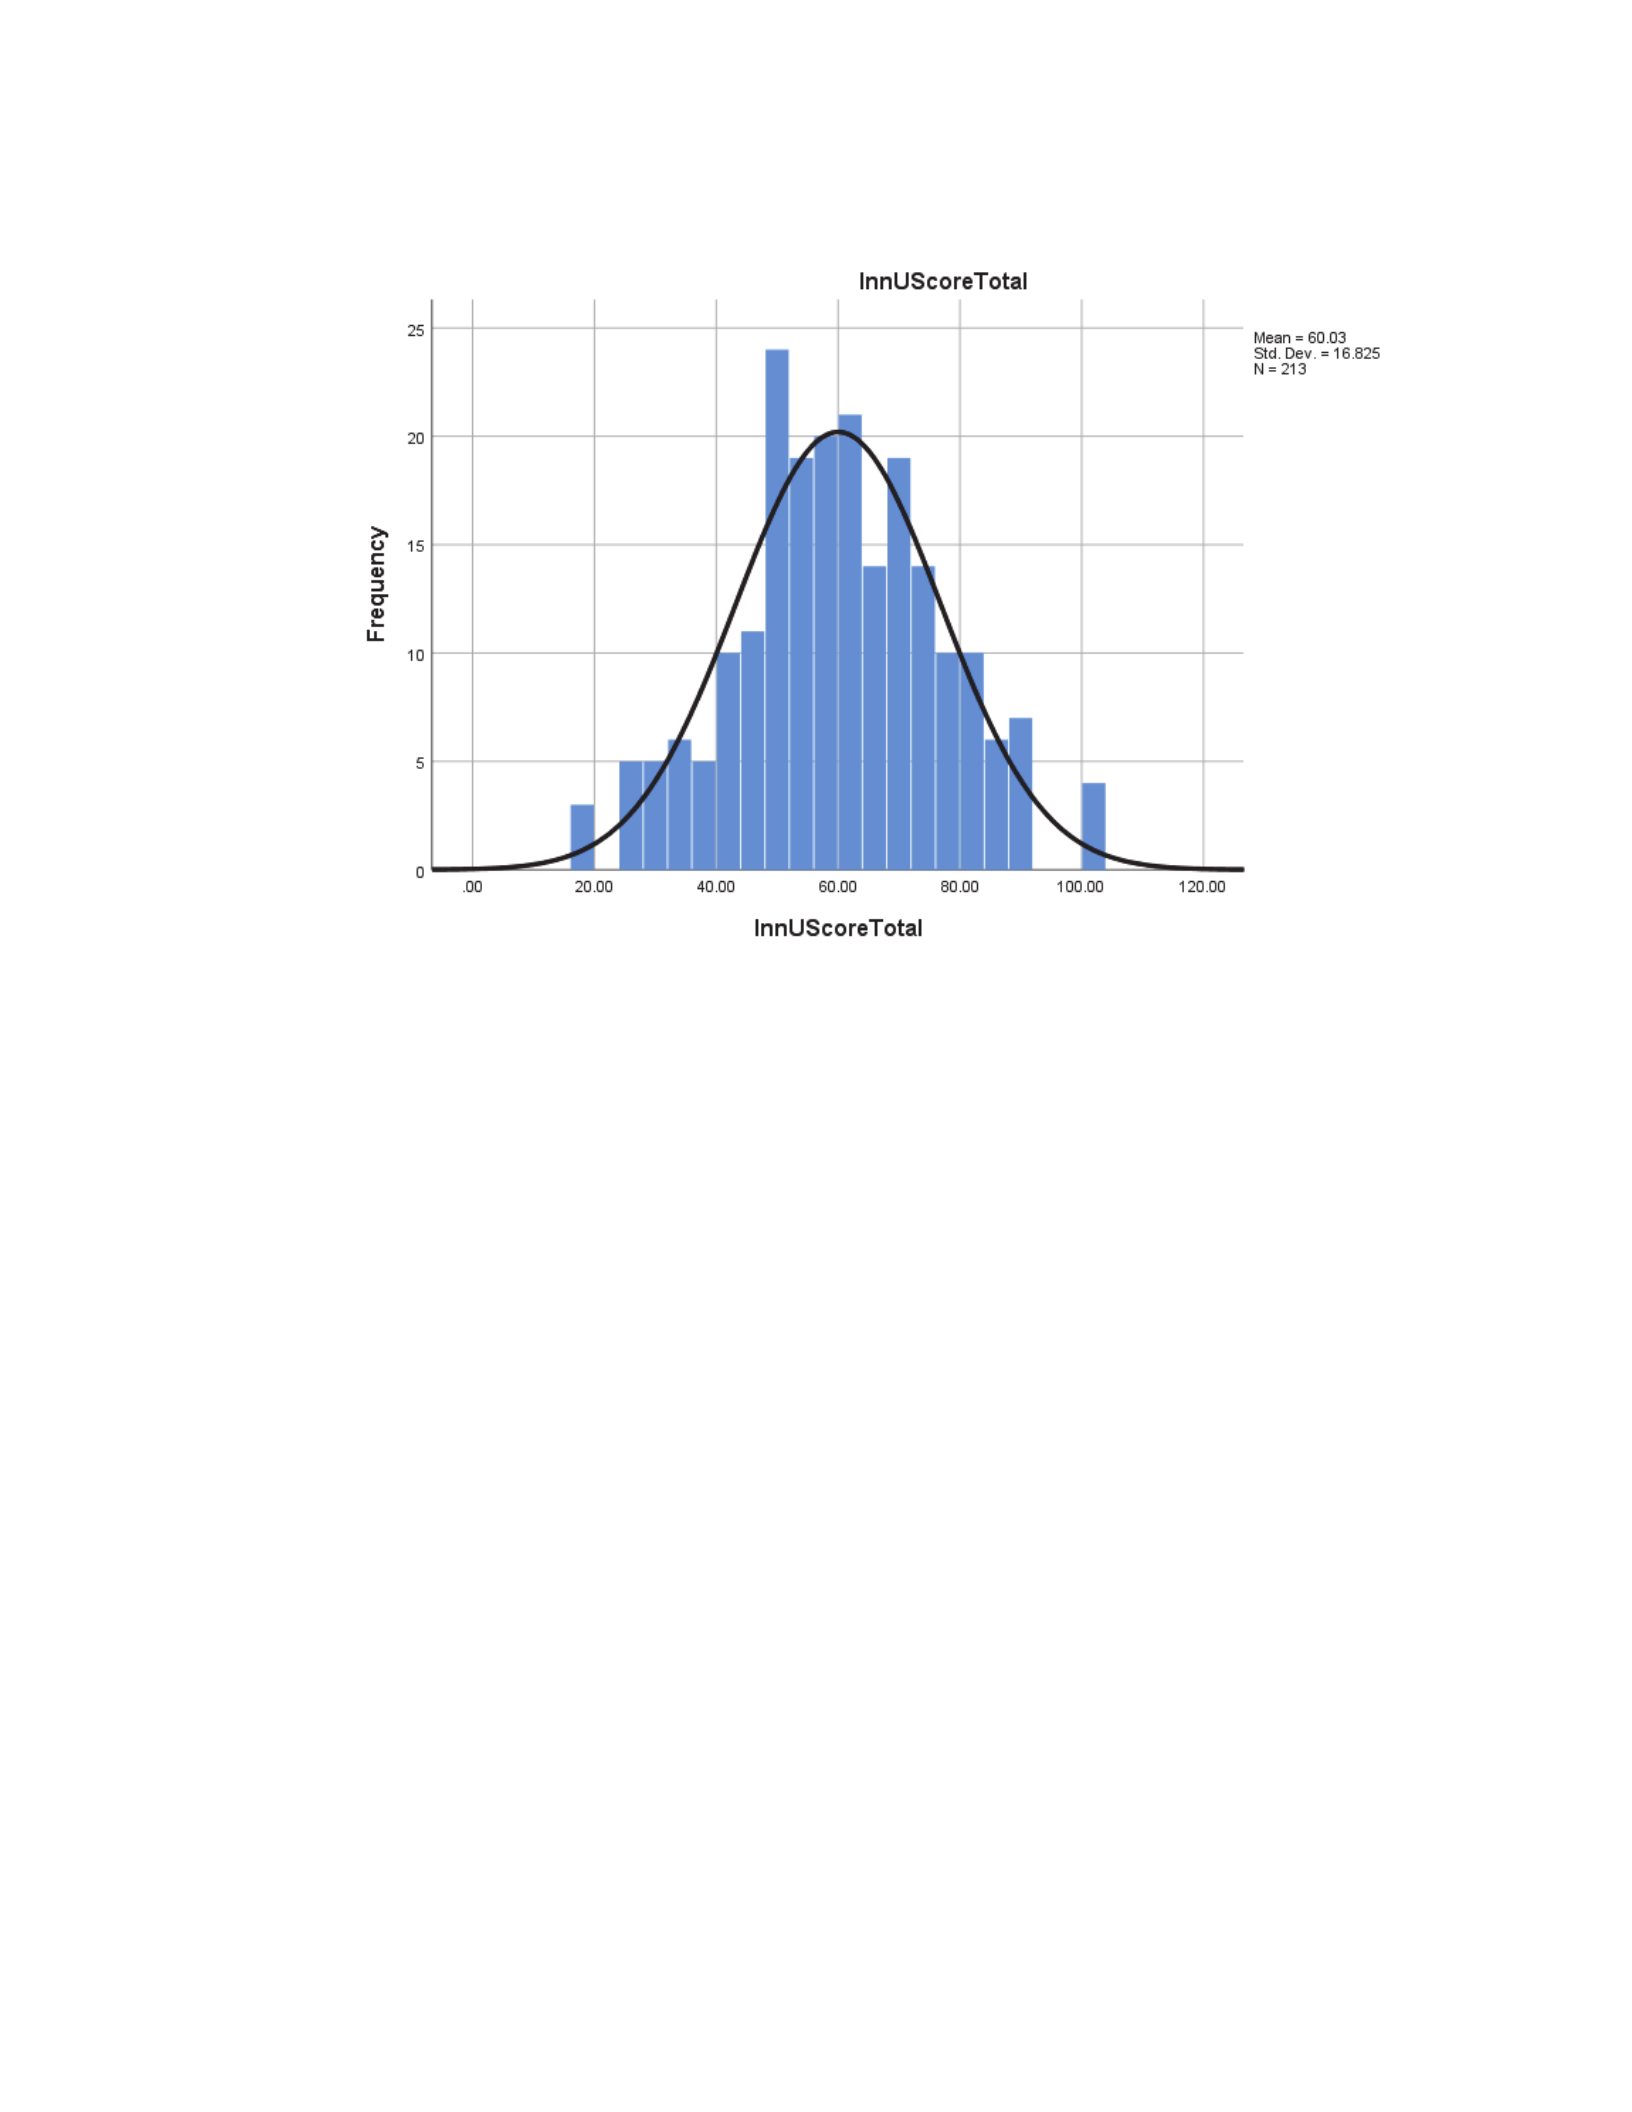
72
Figure 2. Distribution of RO innovation utilization score.
Study Results
Research Question 1 Results
Research Question (RQ) 1: What are the differences in accessibility to innovation
in RO based on location and type of practice in the United States?
H1a0: There is no statistically significant difference in accessibility to
innovation in RO between university and non-university hospitals.
H1a1: There is a statistically significant difference in accessibility to
innovation in RO between university and non-university hospitals.
Dependent variable: innovation score (continuous).
Independent variable: university affiliation (categorical, two levels: has
university affiliation, does not have university affiliation).

73
Results for Hypothesis 1a. An independent t-test was performed to
determine if there were differences in innovation score between university and
non-university centers for the total innovation score and for the innovation
utilization score. There were no outliers in the data, as assessed by inspection of a
boxplot. There was homogeneity of variances, as assessed by Levene’s test for
equality of variances for both the total innovation score (p = 0.689) and the
innovation utilization score (p = 0.129).
The mean innovation score difference for centers with university
affiliation (M = 13.19, SD = 4.76) is higher than the mean innovation score for
centers without a university affiliation (M = 11.55, SD = 4.63), a statistically
significant difference MD = 1.65, 95% CI[0.38,2.917], t(211) = 2.56, p = 0.011, d
= 0.351. Additionally, the patient treatment innovation score for university centers
(M = 3.04, SD = 1.43) is higher than the patient treatment innovation score for
non-university centers (M = 2.64, SD = 1.34), a statistically significant difference
MD = 0.39, 95% CI[0.021,0.76], t(217) = 2.083, p = 0.038, d = 0.282; the
workflow innovation score for university centers (M = 2.96, SD = 1.51) is higher
than the workflow innovation score for non-university centers (M = 2.50, SD =
1.55), a statistically significant difference MD = 0.46, 95% CI[0.05,0.86], t(217) =
2.217, p = 0.028, d = 0.188. Results are presented in Tables 6 and 7. Cohen’s d
was calculated manually.

74
Table 6
Group Statistics for RO center Innovation Score and University Affiliation
Category University
Affiliation N M SD SEM
Patient Positioning Yes 106 2.217 1.087 .106
No 113 2.018 1.035 .097
Patient Treatment Yes 106 3.038 1.434 .139
No 113 2.646 1.349 .127
Treatment
Planning
Yes 106 2.292 1.441 .139
No 113 2.115 1.361 .128
Quality Assurance Yes 106 2.311 1.539 .149
No 113 1.956 1.454 .137
Workflow Yes 106 2.962 1.505 .146
No 113 2.504 1.548 .146
Total Yes 103 13.194 4.757 .469
No 110 11.546 4.635 .442
75
Table 7
Independent Samples T- Test for RO center Innovation Score and University
Affiliation
Category
Levene's Test
for Equality of
Variances
t-test for Equality of Means
F p t df p MD SED
95% CI
LL UL
Patient
Positioning
Equal variances assumed 1.009 .316 1.390 217 .166 .199 .144 -.083 .485
Equal variances not
assumed
1.388 214 .167 .199 .144 -.084 .482
Patient
Treatment
Equal variances assumed .003 .953 2.083 217 .038 .392 .188 .021 .762
Equal variances not
assumed
2.079 211 .039 .392 .188 .0203 .763
Treatment
Planning
Equal variances assumed 1.510 .221 .937 217 .350 .177 .189 -.196 .550
Equal variances not
assumed
.935 214 .351 .177 .189 -.196 .551
Quality
Assurance
Equal variances assumed 1.966 .162 1.758 217 .080 .356 .202 -.043 .754
Equal variances not
assumed
1.755 214 .081 .356 .203 -.044 .755
Workflow
Equal variances assumed 1.152 .284 2.217 217 .028 .458 .207 .051 .865
Equal variances not
assumed
2.219 217 .028 .458 .206 .051 .864
Total
Equal variances assumed .160 .689 2.562 211 .011 1.649 .644 .379 2.917
Equal variances not
assumed
2.559 209 .011 1.649 .644 .379 2.919

76
The mean innovation utilization score for centers with university
affiliation (M = 59.39, SD = 17.74) is similar to the mean innovation utilization
score for centers without a university affiliation (M = 60.62, SD = 15.97). The
innovation utilization score difference is not statistically significant based on
university affiliation. However, for the five categories measured, the mean
workflow innovation utilization score for centers with university affiliation (M =
54.05, SD = 22.85) is higher than the mean workflow innovation utilization score
for centers without a university affiliation (M = 46.95, SD = 19.92), a statistically
significant difference MD = 7.09, 95% CI[0.78,13.39], t(178) = 2.217, p = 0.028,
d = 0.330. Results are presented in Tables 8 and 9. Cohen’s d was calculated
manually. Thus, the null hypothesis H1a,0 is rejected, and the alternate H1a,1 is
accepted.
Table 8
Group Statistics for RO center Innovation Utilization Score and University
Affiliation
Category University
Affiliation N M SD SEM
Patient
Positioning
Yes 90 60.985 25.089 2.645
No 98 63.908 23.681 2.392
Patient Treatment Yes 96 76.195 24.681 2.519
No 102 76.769 25.208 2.496
Treatment
Planning
Yes 91 48.092 26.226 2.749
No 95 51.637 24.973 2.562
Quality
Assurance
Yes 85 56.022 28.503 3.092
No 86 61.565 23.893 2.576
Workflow Yes 90 54.045 22.859 2.410
No 90 46.959 19.921 2.099
Total Yes 103 59.393 17.749 1.749
No 110 60.619 15.970 1.523

77
Table 9
Independent Samples T-Test for RO center Innovation Utilization Score and
University Affiliation
Category
Levene's Test for
Equality of
Variances
t-test for Equality of Means
F p t df p MD SED 95% CI
LL UL
Patient
Positioning
Equal variances
assumed .172 .679 -.822 186 .412 -2.923 3.557 -9.941 4.095
Equal variances
not assumed
-.820 182 .413 -2.923 3.566 -9.956 4.113
Patient
Treatment
Equal variances
assumed .588 .444 -.162 196 .872 -.575 3.546 -7.573 6.423
Equal variances
not assumed
-.162 196 .871 -.575 3.546 -7.568 6.419
Treatment
Planning
Equal variances
assumed .269 .605 -.944 184 .346 -3.545 3.754 -10.952 3.861
Equal variances
not assumed
-.943 182 .347 -3.545 3.758 -10.960 3.869
Quality
Assurance
Equal variances
assumed 3.361 .069 -1.38 169 .170 -5.544 4.020 -13.481 2.392
Equal variances
not assumed
-1.38 163 .170 -5.544 4.024 -13.491 2.402
Workflow
Equal variances
assumed 2.542 .113 2.217 178
.028 7.086 3.196 .771 13.39
Equal variances
not assumed
2.217 175 .028 7.086 3.196 .778 13.40
Total
Equal variances
assumed 2.317 .129 -.531 211 .596 -1.227 2.311 -5.782 3.33
Equal variances
not assumed
-.529 205 .597 -1.227 2.319 -5.798 3.345

78
Hypothesis 1b
H1b0: There is no statistically significant difference in the accessibility to
innovation in RO between metropolitan and non-metropolitan hospitals.
H1b1: There is a statistically significant difference in accessibility to
innovation in RO between metropolitan and non-metropolitan hospitals.
Dependent variable: innovation score (continuous)
Independent variable: urbanicity (categorical, metropolitan, and non-
metropolitan)
Results for Hypothesis 1b. An independent t-test was performed to
determine if there were differences in innovation score between metropolitan and
non-metropolitan centers for the total innovation score and for the innovation
utilization score. There were no outliers in the data, as assessed by inspection of a
boxplot. There was homogeneity of variances, as assessed by Levene’s test for
equality of variances for both the total innovation score (p = 0.478) and the
innovation utilization score (p = 0.855). It is noted that total innovation score was
assessed using binary RUCA categorization 1 and 2-9, while innovation
utilization score was assessed using binary RUCA categorization 1-3 and 4-9.
Results are presented in Tables 10 to 13.
The mean innovation score for metropolitan centers (M = 12.94, SD =
4.65) is similar to the mean innovation score for non-metropolitan centers (M =
11.69, SD = 4.37). The innovation score difference is not statistically significant
based on metropolitan or non-metropolitan status, even though d = 0.275.

79
However, for the five categories measured, the mean patient positioning
innovation score for metropolitan centers (M = 2.21, SD = 1.02) is higher than the
mean patient positioning innovation score for non-metropolitan centers (M =
1.89, SD = 1.12), a statistically significant difference MD = 0.31, 95%
CI[0.011,0.612], t(203) = 2.043, p = 0.042, d = 0.293. Additionally, the mean
patient treatment innovation score for metropolitan centers (M = 3.08, SD = 1.36)
is higher than the mean patient treatment innovation score for non-metropolitan
centers (M = 2.47, SD = 1.33), a statistically significant difference MD = 0.62,
95% CI[0.23,1.00], t(203) = 3.145, p = 0.002, d = 0.457. Results are presented in
Tables 10 and 11. Cohen’s d was calculated manually.
Table 10
Group Statistics for RO center Innovation Score and Urbanicity
Category UrbanicityBinary1 N M SD SEM
Patient Positioning RUCA 1 130 2.208 1.025 .090
RUCA 2-9 75 1.893 1.122 .130
Patient Treatment RUCA 1 130 3.085 1.364 .120
RUCA 2-9 75 2.467 1.340 .155
Treatment Planning RUCA 1 130 2.354 1.375 .121
RUCA 2-9 75 2.000 1.356 .157
Quality Assurance RUCA 1 130 2.169 1.536 .135
RUCA 2-9 75 2.160 1.395 .161
Workflow RUCA 1 130 2.823 1.553 .136
RUCA 2-9 75 2.707 1.431 .165
Total RUCA 1 127 12.937 4.653 .413
RUCA 2-9 72 11.694 4.375 .516

80
Table 11
Independent Samples T-Test for RO center Innovation Score and Urbanicity
Category
Levene's Test for Equality of
Variances t-test for Equality of Means
F p t df p MD SED
95% CI
LL UL
Patient
Positioning
Equal variances
assumed
1.090 .298 2.043 203 .042 .314 .154 .011 .618
Equal variances not
assumed
1.994 143 .048 .314 .158 .003 .626
Patient
Treatment
Equal variances
assumed
.176 .675 3.145 203 .002 .618 .196 .230 1.005
Equal variances not
assumed
3.161 157 .002 .618 .196 .232 1.004
Treatment
Planning
Equal variances
assumed
.536 .465 1.784 203 .076 .354 .198 -.037 .745
Equal variances not
assumed
1.791 156.273 .075 .354 .198 -.036 .744
Quality
Assurance
Equal variances
assumed
1.997 .159 .043 203 .966 .009 .216 -.416 .434
Equal variances not
assumed
.044 167 .965 .009 .210 -.405 .424
Workflow
Equal variances
assumed
3.040 .083 .532 203 .595 .116 .219 -.315 .548
Equal variances not
assumed
.544 165 .587 .116 .214 -.306 .539
Total
Equal variances
assumed
.505 .478 1.849 197 .066 1.243 .672 -.083 2.568
Equal variances not
assumed
1.881 155 .062 1.243 .660 -.062 2.547

81
The mean innovation utilization score for metropolitan centers (M =
60.73, SD = 16.67) is similar to the mean innovation utilization score for non-
metropolitan centers (M = 55.41, SD = 15.38). The total innovation utilization
score difference is not statistically significant based on metropolitan or non-
metropolitan status, even though d = 0.331. However, for the five categories
measured, the mean patient positioning innovation utilization score for
metropolitan centers (M = 63.96, SD = 23.78) is higher than the mean patient
positioning innovation utilization score for non-metropolitan centers (M = 47.73,
SD = 29.28), a statistically significant difference MD = 16.22, 95%
CI[0.73,31.72], t(173) = 2.067, p = 0.04, d = 0.608. Results are presented in
Tables 12 and 13. Cohen’s d was calculated manually. Thus, the null hypothesis
H1b,0 is rejected, and the alternate H1b,1 is accepted.

82
Table 12
Group Statistics for RO center Innovation Utilization Score and Urbanicity
Category UrbanicityBinary2
N M SD SEM
Patient Positioning RUCA 1-3 165 63.958 23.784 1.852
RUCA 4-9 10 47.733 29.287 9.262
Patient Treatment RUCA 1-3 175 78.023 23.493 1.776
RUCA 4-9 11 72.897 25.561 7.707
Treatment
Planning
RUCA 1-3 166 50.171 25.228 1.958
RUCA 4-9 11 43.606 28.433 8.573
Quality Assurance RUCA 1-3 152 57.803 25.949 2.105
RUCA 4-9 11 69.955 25.739 7.761
Workflow RUCA 1-3 164 50.896 21.894 1.710
RUCA 4-9 8 40.042 18.073 6.390
Total RUCA 1-3 186 60.726 16.673 1.223
RUCA 4-9 13 55.416 15.385 4.267

83
Table 13
Independent Samples T- Test for RO center Innovation Utilization Score and
Urbanicity
Category
Levene's
Test for
Equality of
Variances
t-test for Equality of Means
F p t df p MD SED
95% CI
LL UL
Patient
Positioning
Equal variances assumed 1.463 .228 2.067 173 .040 16.22 7.849 .732 31.72
Equal variances not
assumed
1.718 10 .117 16.22 9.445 -4.90 37.35
Patient
Treatment
Equal variances assumed .067 .795 .698 184 .486 5.13 7.339 -9.35 19.61
Equal variances not
assumed
.648 11 .530 5.13 7.909 -12.3 22.52
Treatment
Planning
Equal variances assumed .221 .639 .829 175 .408 6.56 7.915 -9.06 22.19
Equal variances not
assumed
.747 11 .471 6.56 8.794 -12.8 25.91
Quality
Assurance
Equal variances assumed .043 .836 -1.50 161 .135 -12.15 8.098 -28.1 3.84
Equal variances not
assumed
-1.51 12 .158 -12.15 8.041 -29.8 5.45
Workflow
Equal variances assumed .214 .644 1.379 170 .170 10.86 7.875 -4.69 26.40
Equal variances not
assumed
1.641 8 .139 10.86 6.614 -4.38 26.09
Total
Equal variances assumed .034 .855 1.115 197 .266 5.310 4.762 -4.1 14.70
Equal variances not
assumed
1.196 14 .251 5.310 4.439 -4.2 14.83

84
Research Question 2 Results
Research Question (RQ) 2: What are the statistically significant factors
(demographics, practice details, context-specific psychological
antecedents) that predict the accessibility to innovation in the RO clinic?
H20: There are no statistically significant factors predicting innovation
score.
H21: There are statistically significant factors predicting innovation score.
Dependent variable: innovation score (continuous).
Independent variables: reporting structure, size of physics group, age,
gender, DABR status, residency status, meeting attendance, education
level, leadership, (categorical) appreciation, and motivation (continuous).
Bivariate analysis for appreciation, motivation, and number of
meetings. The Shapiro-Wilk test for normality was performed for innovation
score and innovation utilization score using appreciation, motivation, and number
of meetings as factors (continuous variables). The results of the Shapiro-Wilk test
were statistically significant for all three parameters (p < 0.001). Thus, the data
are not normally distributed. The Q-Q plots were also not normal. Spearman
correlation was used to perform bivariate analysis for appreciation and
motivation. There was a positive correlation between innovation utilization and
participant appreciation (rs = 0.224, p = 0.002) and motivation (rs = 0.215, p =
0.003). Both correlations are of small to medium effect size class, according to
Cohen’s criteria (Ellis, 2010). There was a small negative correlation between

85
innovation utilization and the number of meetings attended (rs = -0.186, p =
0.013). Since this result is unexpected, the relationship with total innovation score
was also investigated. Results were not statistically significant (rs = 0.067, p =
0.371). Thus, the number of meetings will not be included in the final regression
model.
Bivariate analysis for gender, opinion leadership, education, and
residency status. The Shapiro-Wilk test for normality was performed for
innovation score and innovation utilization score using gender, opinion
leadership, education, and residency as factors (binary variables). The results of
the Shapiro-Wilk test were not statistically significant for gender (p = 0.433),
opinion leadership (p = 0.172), education (p = 0.922), and residency (p = 0.981).
Thus, the data are normally distributed. The Q-Q plots were also normal. An
independent sample t-test was performed for gender, opinion leadership,
education, and residency. Results were not statistically significant for gender (p =
0.828), opinion leadership (p = 0.921), and residency (p = 0.402). Results were
statistically significant for education. The mean innovation utilization score for
Master’s degree (M = 61.42, SD = 16.11) is higher than the mean innovation
utilization score for Doctoral degree (M = 56.37, SD = 17.22), a statistically
significant difference MD = 5.06, 95% CI[0.18,9.94], t(188) = 2.046, p = 0.042, d
= 0.278.
Bivariate analysis for age, DABR status, number of meetings,
reporting structure, and number of physicists. The Shapiro-Wilk test for

86
normality was performed for innovation score and innovation utilization score
using age, DABR status, number of meetings, reporting structure, and number of
physicists as factors (categorical variables). The results of the Shapiro-Wilk test
were not statistically significant for meetings (p = 0.425), age (p = 0.768), DABR
status (p = 0.573), reporting structure (p = 0.739), and the number of physicists (p
= 0.431). There was no statistically significant effect of age (p = 0.38), DABR
status (p = 0.10), reporting status (p = 0.06), and the number of physicists in
practice (p = 0.57).
Binary logistic regression. Three parameters were found to be
statistically significant in affecting innovation implementation: degree,
motivation, and appreciation. Since the two latter are non-linear, a binomial
logistic regression was performed. The dependent variable, innovation utilization,
was recoded to binary (1 = below median, 2 = above median, Mdn = 60.03).
Linearity of the continuous variables with respect to the logit of the dependent
variable was assessed using the Box-Tidwell procedure. The interaction term was
not statistically significant for motivation (p = 0.587), and for appreciation (p =
0.338), thus these two independent variables are linearly related to the logit of the
dependent variable. No corrections were applied. Results of the binary logistic
regression are presented in Tables 14 to 18.

87
Table 14
Binary Logistic Regression Omnibus Tests of Model Coefficients
χ2df p
Step 1 Step 10.861 3 .013
Block 10.861 3 .013
Model 10.861 3 .013
Table 15
Binary Logistic Regression Model Summary
Step -2 Log likelihood Cox & Snell R Square Nagelkerke R Square
1 250.720a .056 .075
a. Estimation terminated at iteration number 3 because parameter estimates changed by less than
.001.
Table 16
Binary Logistic Regression Hosmer and Lemeshow Test
Step χ2 df p
1 6.187 8 .626
Table 17
Binary Logistic Regression Classification Table
Observed Predicted
Innovation Utilization Score
Below
Median
Above
Median
Percent
Correct
Step 1 Innovation
Utilization Score
Below
Median 60 34 65.7
Above
Median 40 50 55.6
Overall
Percentage 60.8
a. The cut value is .500

88
Table 18
Binary Logistic Regression Results and Variables in the Equation for Innovation
Utilization (outcome variable)
B S.E. Wald df p OR
95% CI.for
OR
LL UL
Step
1a
Education -.600 .315 3.620 1 .057 .549 .296 1.018
Appreciation .013 .008 2.385 1 .122 1.013 .997 1.030
Motivation .001 .009 .005 1 .944 1.001 .983 1.019
Constant -.821 .560 2.151 1 .142 .440
a. Variable(s) entered on step 1: Education, Appreciation, Motivation.
There were no cases with studentized residuals greater than 2.0. The
Hosmer and Lemeshow Test was not statistically significant (p = 0.626), thereby
suggesting a model fit. The logistic regression model was statistically significant,
χ2(3) = 10.861, p = 0.013. The model explained 7.5% (Nagelkerke R2) of the
variance in innovation utilization and correctly classified 60.8% of cases.
Sensitivity was 55.6%, specificity was 65.7%, positive predictive value was
59.5%, and the negative predictive value was 38.1%. None of the predictor
variables was statistically significant. Thus, the null hypothesis H2,0 is accepted,
and the alternate H2,1 is rejected.
Research Question 3 Results
RQ 3: What are the statistically significant barriers that MPs practicing in RO in
the United States face in implementing innovations?
H30: There are no statistically significant barriers affecting innovation
score.

89
H31: There are statistically significant barriers affecting innovation score.
Dependent variable: innovation score (continuous).
Independent variables: barriers (continuous).
Seven measured barriers across five categories and in total were assessed
for normality. The results of the Shapiro-Wilk test were mixed, with some values
being statistically significant, and some not being statistically significant (data not
shown). Thus, the data are assumed to not be normally distributed as a group. The
Q-Q plots were also not normal. The seven parameters used to assess barriers
were assessed for the reliability of the construct. The scale had a high level of
internal consistency, as determined by a Cronbach's alpha of 0.882. Spearman
correlation was used to perform bivariate analysis across each category and in
total. Spearman’s rho results are presented in Tables 19 to 25.
There are statistically significant barriers in patient treatment, treatment
planning, quality assurance, workflow, and innovation utilization total. Lack of
interest is a small statistically significant barrier in patient treatment innovation
utilization (rs = 0.199, p<0.05). Lack of inter-operability is a small statistically
significant barrier in workflow innovation utilization (rs = 0.218, p<0.05). Lack of
time and staffing is a small statistically significant barrier in quality assurance
innovation utilization (rs = -0.178, p<0.05). The negative correlation sign is noted
and will be further discussed in Chapter 5. There are multiple small statistically
significant barriers in treatment planning, such as lack of evidence (rs = 0.203,
p<0.05), complexity (rs = 0.175, p<0.05), lack of time and staffing (rs = 0.237,

90
p<0.01), lack of inter-operability (rs = 0.203, p<0.05), and lack of reimbursement
(rs = 0.269, p<0.01). There are multiple small statistically significant barriers in
total innovation utilization, such as lack of evidence (rs = 0.161, p<0.05), lack of
interest (rs = 0.264, p<0.01), lack of inter-operability (rs = 0.214, p<0.01), and
lack of reimbursement (rs = 0.176, p<0.05). All statistically significant
correlations in the study were of small to medium effect size class, according to
Cohen’s definition (Ellis, 2010). Thus, the null hypothesis H3,0 is rejected, and the
alternate H3,1 is accepted.

91
Table 19
Correlations for Barriers in RO Patient Positioning Innovation Utilization
Innovation
Utilization
Score Evidence Complexity
Time/
Staffing
Training/
Support Interest
Inter
Operability Reimbursement
Innovation
Utilization
Score
rs 1.000 -.010 -.084 -.014 -.008 .005 .040 .068
P . .915 .331 .870 .929 .949 .644 .459
N 188 118 135 149 131 144 138 121
Evidence rs -.010 1.000 .475** .199* .441** .279** .271** .272**
P .915 . .000 .032 .000 .003 .005 .007
N 118 127 115 116 109 111 107 96
Complexity rs -.084 .475** 1.000 .430** .553** .265** .352** .161
P .331 .000 . .000 .000 .003 .000 .093
N 135 115 146 134 119 125 123 110
Time/
Staffing
rs -.014 .199* .430** 1.000 .535** .387** .208* .218*
P .870 .032 .000 . .000 .000 .018 .018
N 149 116 134 165 136 142 130 117
Training/
Support
rs -.008 .441** .553** .535** 1.000 .527** .404** .299**
P .929 .000 .000 .000 . .000 .000 .002
N 131 109 119 136 142 128 117 105
Interest rs .005 .279** .265** .387** .527** 1.000 .432** .357**
P .949 .003 .003 .000 .000 . .000 .000
N 144 111 125 142 128 162 131 119
Inter
Operability
rs .040 .271** .352** .208* .404** .432** 1.000 .469**
P .644 .005 .000 .018 .000 .000 . .000
N 138 107 123 130 117 131 150 111
Reimbursement rs .068 .272** .161 .218* .299** .357** .469** 1.000
P .459 .007 .093 .018 .002 .000 .000
N 121 96 110 117 105 119 111 134
*. Correlation is significant at the 0.05 level (2-tailed).
**. Correlation is significant at the 0.01 level (2-tailed).

92
Table 20
Correlations for Barriers in RO Patient Treatment Innovation Utilization
Innovation
Utilization
Score Evidence Complexity
Time/
Staffing
Training/
Support Interest
Inter
Operability Reimbursement
Innovation
Utilization
Score
rs 1.000 .187 -.009 .032 .054 .199*.170 .177
P . .066 .927 .721 .595 .030 .086 .085
N 198 97 118 129 101 119 103 96
Evidence rs .187 1.000 .560** .452** .547** .426** .413** .385**
P .066 ..000 .000 .000 .000 .000 .001
N 97 102 91 91 82 86 82 75
Complexity rs -.009 .560** 1.000 .534** .664** .270** .471** .402**
P .927 .000 ..000 .000 .007 .000 .000
N 118 91 122 112 95 99 93 86
Time/
Staffing
rs .032 .452** .534** 1.000 .558** .367** .280** .364**
P .721 .000 .000 ..000 .000 .005 .000
N 129 91 112 132 100 106 98 90
Training/
Support
rs .054 .547** .664** .558** 1.000 .455** .545** .407**
P .595 .000 .000 .000 ..000 .000 .000
N 101 82 95 100 105 92 86 80
Interest rs .199* .426** .270** .367** .455** 1.000 .474** .519**
P .030 .000 .007 .000 .000 ..000 .000
N 119 86 99 106 92 122 95 85
Inter
Operability
rs .170 .413** .471** .280** .545** .474** 1.000 .513**
P .086 .000 .000 .005 .000 .000 . .000
N 103 82 93 98 86 95 107 83
Reimbursement rs .177 .385** .402** .364** .407** .519** .513** 1.000
P .085 .001 .000 .000 .000 .000 .000 .
N 96 75 86 90 80 85 83 100
*. Correlation is significant at the 0.05 level (2-tailed).
**. Correlation is significant at the 0.01 level (2-tailed).

93
Table 21
Correlations for Barriers in RO Treatment Planning Innovation Utilization
Innovation
Utilization
Score Evidence Complexity
Time/
Staffing
Training/
Support Interest
Inter
Operability Reimbursement
Innovation
Utilization
Score
rs 1.000 .203*.175*.092 .237** .129 .203* .269**
P . .030 .042 .255 .005 .140 .030 .004
N 186 115 135 155 136 133 114 111
Evidence rs .203* 1.000 .361** .308** .456** .344** .529** .357**
P .030 ..000 .001 .000 .000 .000 .001
N 115 119 107 112 102 105 91 91
Complexity rs .175* .361** 1.000 .470** .495** .392** .517** .532**
P .042 .000 ..000 .000 .000 .000 .000
N 135 107 143 138 126 120 101 98
Time/
Staffing
rs .092 .308** .470** 1.000 .580** .426** .295** .477**
P .255 .001 .000 ..000 .000 .002 .000
N 155 112 138 163 135 131 108 108
Training/
Support
rs .237** .456** .495** .580** 1.000 .399** .574** .376**
P .005 .000 .000 .000 ..000 .000 .000
N 136 102 126 135 144 120 105 100
Interest rs .129 .344** .392** .426** .399** 1.000 .477** .543**
P .140 .000 .000 .000 .000 ..000 .000
N 133 105 120 131 120 145 105 101
Inter
Operability
rs .203* .529** .517** .295** .574** .477** 1.000 .522**
P .030 .000 .000 .002 .000 .000 . .000
N 114 91 101 108 105 105 119 90
Reimbursement rs .269** .357** .532** .477** .376** .543** .522** 1.000
P .004 .001 .000 .000 .000 .000 .000 .
N 111 91 98 108 100 101 90 119
*. Correlation is significant at the 0.05 level (2-tailed).
**. Correlation is significant at the 0.01 level (2-tailed).

94
Table 22
Correlations for RO Quality Assurance Innovation Utilization
Innovation
Utilization
Score Evidence Complexity
Time/
Staffing
Training/
Support Interest
Inter
Operability Reimbursement
Innovation
Utilization
Score
rs 1.000 .124 .037 -.178*-.083 -.168 -.105 -.027
P . .225 .707 .036 .388 .059 .264 .800
N 171 97 108 140 110 128 116 91
Evidence rs .124 1.000 .503** .383** .470** .377** .466** .338**
P .225 ..000 .000 .000 .000 .000 .002
N 97 108 90 99 87 96 92 81
Complexity rs .037 .503** 1.000 .531** .582** .355** .442** .312**
P .707 .000 ..000 .000 .000 .000 .005
N 108 90 117 113 101 99 97 78
Time/
Staffing
rs -.178* .383** .531** 1.000 .651** .538** .490** .222*
p .036 .000 .000 ..000 .000 .000 .038
N 140 99 113 155 115 130 114 88
Training/
Support
rs -.083 .470** .582** .651** 1.000 .626** .573** .234*
p .388 .000 .000 .000 ..000 .000 .042
N 110 87 101 115 120 105 95 76
Interest rs -.168 .377** .355** .538** .626** 1.000 .507** .482**
p .059 .000 .000 .000 .000 ..000 .000
N 128 96 99 130 105 147 107 89
Inter
Operability
rs -.105 .466** .442** .490** .573** .507** 1.000 .416**
p .264 .000 .000 .000 .000 .000 . .000
N 116 92 97 114 95 107 125 80
Reimbursement rs -.027 .338** .312** .222*.234*.482** .416** 1.000
p .800 .002 .005 .038 .042 .000 .000 .
N 91 81 78 88 76 89 80 102
*. Correlation is significant at the 0.05 level (2-tailed).
**. Correlation is significant at the 0.01 level (2-tailed).

95
Table 23
Correlations for RO Workflow Innovation Utilization
Innovation
Utilization
Score Evidence Complexity
Time/
Staffing
Training/
Support Interest
Inter
Operability Reimbursement
Innovation
Utilization
Score
rs 1.000 .111 .118 -.051 -.050 -.034 .210* -.034
p . .303 .209 .525 .581 .679 .033 .746
N 180 88 115 155 125 149 103 91
Evidence rs .111 1.000 .420** .295** .411** .546** .543** .387**
p .303 ..000 .006 .000 .000 .000 .001
N 88 91 87 86 85 82 80 75
Complexity rs .118 .420** 1.000 .475** .642** .278** .539** .309**
p .209 .000 ..000 .000 .003 .000 .004
N 115 87 120 115 103 109 92 84
Time/
Staffing
rs -.051 .295** .475** 1.000 .625** .497** .202* .407**
p .525 .006 .000 ..000 .000 .042 .000
N 155 86 115 161 122 146 102 92
Training/
Support
rs -.050 .411** .642** .625** 1.000 .486** .437** .319**
p .581 .000 .000 .000 ..000 .000 .003
N 125 85 103 122 130 119 98 83
Interest rs -.034 .546** .278** .497** .486** 1.000 .278** .428**
p .679 .000 .003 .000 .000 ..005 .000
N 149 82 109 146 119 156 101 89
Inter
Operability
rs .210* .543** .539** .202*.437** .278** 1.000 .352**
p .033 .000 .000 .042 .000 .005 . .002
N 103 80 92 102 98 101 106 74
Reimbursement rs -.034 .387** .309** .407** .319** .428** .352** 1.000
p .746 .001 .004 .000 .003 .000 .002 .
N 91 75 84 92 83 89 74 95
*. Correlation is significant at the 0.05 level (2-tailed).
**. Correlation is significant at the 0.01 level (2-tailed).

96
Table 24
Correlations for RO Innovation Utilization Score Total
Innovation
Utilization
Score Evidence Complexity
Time/
Staffing
Training/
Support Interest
Inter
Operability Reimbursement
Innovation
Utilization
Score
rs 1.000 .161*.085 .111 .027 .264** .214** .176*
p . .038 .254 .120 .722 .000 .005 .025
N 213 166 183 199 180 195 174 162
Evidence rs .161* 1.000 .458** .353** .517** .391** .495** .445**
p .038 ..000 .000 .000 .000 .000 .000
N 166 166 159 165 155 161 152 145
Complexity rs .085 .458** 1.000 .424** .596** .252** .478** .372**
p .254 .000 ..000 .000 .001 .000 .000
N 183 159 183 183 169 177 164 150
Time/
Staffing
rs .111 .353** .424** 1.000 .609** .500** .393** .394**
p .120 .000 .000 ..000 .000 .000 .000
N 199 165 183 199 178 191 171 159
Training/
Support
rs .027 .517** .596** .609** 1.000 .469** .505** .355**
p .722 .000 .000 .000 ..000 .000 .000
N 180 155 169 178 180 173 160 149
Interest rs .264** .391** .252** .500** .469** 1.000 .384** .435**
p .000 .000 .001 .000 .000 ..000 .000
N 195 161 177 191 173 195 165 157
Inter
Operability
rs .214** .495** .478** .393** .505** .384** 1.000 .569**
p .005 .000 .000 .000 .000 .000 . .000
N 174 152 164 171 160 165 174 147
Reimbursement rs .176* .445** .372** .394** .355** .435** .569** 1.000
p .025 .000 .000 .000 .000 .000 .000 .
N 162 145 150 159 149 157 147 162
*. Correlation is significant at the 0.05 level (2-tailed).
**. Correlation is significant at the 0.01 level (2-tailed).

97
Table 25
Summary of RO Barrier Coefficients in all Categories for MPs
Patient
positioning
Patient
Treatment
Treatment
Planning QA Workflow Total
Evidence 0.203* 0.161*
Complexity 0.175*
Time/Staffing 0.237**
-
0.178*
Training/Support
Interest 0.199* 0.264**
Interoperability 0.203* 0.218* 0.214**
Reimbursement 0.269** 0.176*
*. Correlation is significant at the 0.05 level (2-tailed).
**. Correlation is significant at the 0.01 level (2-tailed).
Summary
The three research questions posed were answered. The null hypotheses
H1a, H1b, and H3were rejected, and null hypothesis H2 was accepted. There are
statistically significant differences in the accessibility of innovative services based
on hospital university affiliation and urbanicity, with more innovative services
being available to patients treated in urban, university hospitals. There are
statistically significant predicting factors that affect the accessibility of innovative
services, with MP appreciation and motivation having a weak predictive
relationship with increased accessibility of innovative services, albeit the model is
not statistically significant. There are statistically significant barriers MPs face in
providing access to innovative services to patients. In Chapter 5 there will be a

98
detailed discussion on the implications of these results and recommendations for
future research.

99
Chapter 5: Discussion, Conclusions, and Recommendations
Introduction
The purpose of this study was to investigate the accessibility of innovative
services in RO in the United States and assess possible diffusion patterns using an
online survey of MPs practicing in the United States. The dependent variable was
innovation score. Independent variables were geographic location; practice details
(university affiliation, reporting structure, and size of physics group);
demographics (age, gender, DABR status, residency status, meeting attendance,
and education level); and context-specific psychological antecedents (motivation,
appreciation, and leadership).
There were statistically significant differences in the accessibility of
innovative services based on hospital university affiliation and urbanicity, with
more innovative services being available to patients treated in urban, university
hospitals. Also, there are statistically significant predicting factors that affect the
accessibility of innovative services, with MP appreciation and motivation having
a weak predictive relationship with increased accessibility of innovative services.
Finally, there were statistically significant barriers in patient treatment, treatment
planning, quality assurance, and workflow. Findings indicate that MPs face
challenges in providing access to innovative services to patients. In this chapter,
the results are discussed in context, the study limitations, and recommendations
for future research are made. The chapter concludes with a conclusion to the
study.

100
Sample Characteristics
Known proportions of organizational and personal characteristics were
retrieved from the most recent salary survey for RO MPs (American Association
of Physicists in Medicine, 2018). This report lists primary employment settings as
private or community hospital, government hospital, medical school or university
hospital, college or university, government hospital, medical physics service
group, physician group, industrial or commercial firm, and cancer center. It is
unclear if some categories are correlated--for example, there can be a cancer
center with a university affiliation. This self-identification can be subjective; this
is the reason this classification was not selected for this study. The report is
useful, however, in providing some baseline descriptive statistics. Based on this
report, 17% of master’s-level MPs work in centers with university affiliation, and
83% of PhD physicists work in centers with university affiliation. On average,
50% of MPs are employed by centers with a university affiliation, 26% of MPs
are women, 55% hold a master’s degree, 89% are certified by the ABR, and 28%
graduated from a residency.
In analyzing the sample descriptive statistics and comparison to known
proportions, it is concluded that there are similarities in percentages of university
affiliation, type of degree, and DABR status, but not for gender and residency.
The respondent gender ratio was higher for male and higher for residency
graduates. There are no publicly available proportions for age distribution, but the
respondent age distribution appears to be skewed towards younger respondents,

101
which is in alignment with the higher response rate for residency graduates. No
exact known proportions are known for urbanicity, meetings attended, reporting
structure, number of physicists, volunteer status, appreciation or motivation. It is
thus concluded that the sample was overall representative of the population.
Open-Ended Feedback
The study included a free-text comment section at the end of the survey.
Many of the comments revolved around the cost of innovation, which was
expected. An unexpected common thread, however, was concerns about
maintaining safety. MP participants were highly concerned that using innovations
and changing the status quo might be inconsistent with maintaining patient safety.
This finding was unexpected because all innovations in question are FDA-
approved and commercially available. The pathway to deteriorating safety would
be possible only through poor implementation. This circles back to workflow
innovation. A conclusion is that MPs do not feel innovation improves patient
safety and/or they do not know how to safely implement innovations in the clinic.
Interpretation of the Findings
University Affiliation and Innovation
In Research Question 1a it was demonstrated that centers with a university
affiliation have a higher mean innovation score than centers without a university
affiliation (MD = 1.65, 95% CI [0.38,2.917], t(211) = 2.56, p = 0.011, d = 0.351).
As discussed in the literature review in Chapter 2, there are many outcome
differences between academic and nonacademic centers. While the difference in

102
innovation score is likely not the only factor contributing to outcome differences,
it is a factor that needs to be incorporated in future models. The results of this
study are in congruence with similar studies performed in the United States (see
Pfister et al., 2015). It is interesting to note that the two categories with
statistically significant results are patient treatment and workflow. The parameters
affecting the patient treatment innovation score (stereotactic body radiosurgery,
stereotactic cranial radiosurgery, robotic radiosurgery, intraoperative radiation
therapy, and flattening free beams) are techniques that are only available in newer
accelerators, which are in their majority multimillion-dollar investments.
In Research Question 1a it was also demonstrated that centers with
university affiliation have a higher mean workflow utilization score than centers
without a university affiliation (MD = 7.09, 95% CI [0.78,13.39], t(178) = 2.217,
p = 0.028, d = 0.330). This finding is interesting because organizational
innovation has not previously been studied in RO in the United States, as typically
publications focus on technological differences (see Chen, 2014)). The results of
this study are in congruence with the published results from the Netherlands (M.
Jacobs, 2017). Improving workflows can be a low-risk, high-yield opportunity for
many centers lacking the funds for large investments. A curriculum with core and
adjunct tools for MPs is currently under development through the Medical
Physics Leadership Academy Working Group (J. Johnson, personal
communication, MPLAW Retreat, May 2019). The lack of statistically significant
differences in other categories is a positive finding for the industry, as it implies

103
that once centers break through the barrier of purchasing innovative technologies,
there are no major differences in utilizing them.
Urbanicity and Innovation
In Research Question 1b it was demonstrated that urban centers have a
higher innovation scores in patient positioning (MD = 0.31, 95% CI
[0.011,0.612], t(203) = 2.043, p = 0.042, d = 0.293) and patient treatment (MD =
0.62, 95% CI [0.23,1.00], t(203) = 3.145, p = 0.002, d = 0.457). Thus, the results
of this study are in congruence with similar studies performed in the United States
(Charlton et al., 2015). The quantitative assessment did not reveal large
differences for total innovation, which was an unexpected result. This is possibly
due either to the low power of the study or the RUCA classification that was used
in this study; greater granularity may be necessary. The results were plotted on a
map of the United States for qualitative analysis, as shown in Figure 3. The
population was superimposed with innovation score (darker green, higher
population). Additionally, all RO the centers that are currently operational in the
United States are superimposed as black squares (IAEA DIRAC database, 2018).
The heatmap represents centers that are more innovative (red) versus less
innovative (blue). The most innovative centers are in close proximity and in areas
with high population density. Conversely, areas with low population density have
the lowest innovation score. This qualitative assessment does support the claim
that urban centers provide more innovative treatments, despite the absence of
large effect sizes and statistical significance.
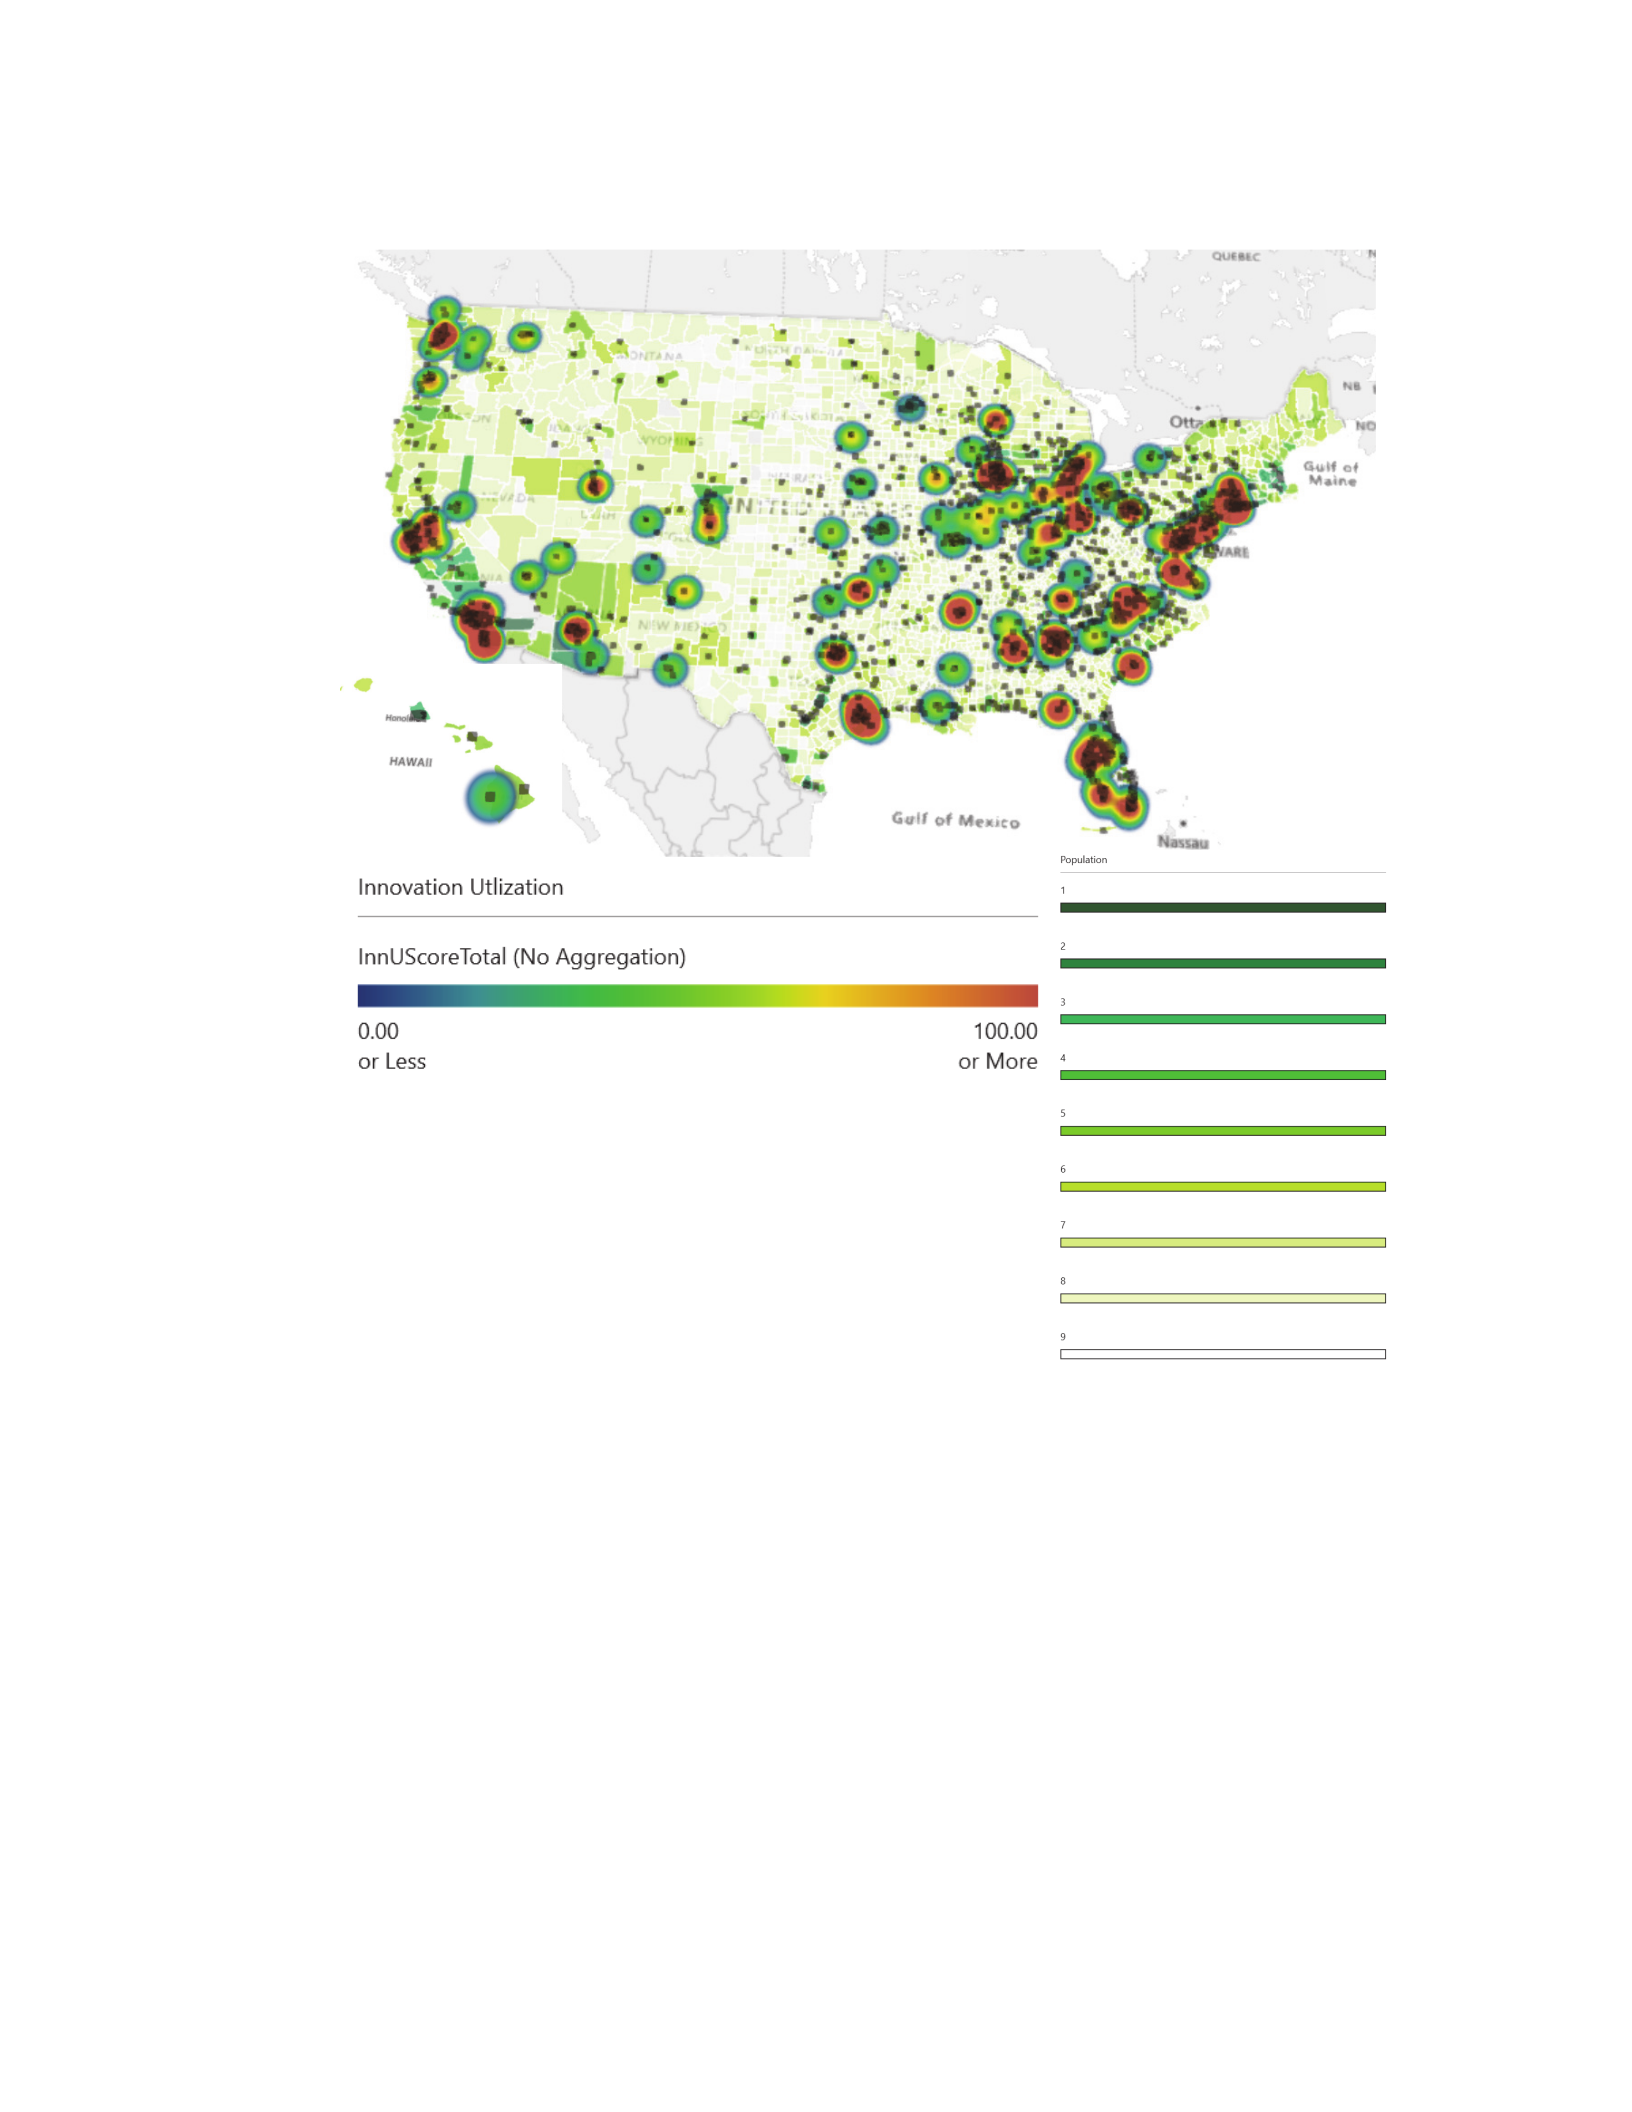
104
Figure 3. Map of the United States with innovation utilization score. Hawaii is
not to scale. No data were received for Alaska. Map layers include population
density as shades of green and RO centers as squares.

105
While differences in patient treatment are relatively easy to explain due to
purchasing decision and competition in urban centers, the differences in patient
positioning may not be so obvious. Patient positioning is typically decided at the
time of simulation and is the primary responsibility of the radiation therapists.
Historically there is great variation in MPs involvement in patient positioning and
setup reproducibility, with some MPs being very involved, and some MPs being
absent in the simulation process (Clements et al., 2018). The introduction of
mandatory MP residencies is closing this gap. The increase in hypo-fractionated
treatments has also changed this dynamic, as discussed in the 2014 AAPM
summer school on “safely and accurately delivering high precision, hypo-
fractionated treatments” and AAPM reports (Halvorsen et al., 2017). However,
there may be discordance of information flowing to the American Society of
Radiologic Technologists. Another possible explanation is that in urban centers,
patients “shop around” for their treatment, with higher socioeconomic status
patients often requesting or demanding certain types of treatment (Martin,
Thomas, Harden, & Burnet, 2015; Roubou & Alexopoulou, 2015). Frequent
examples from personal experience include prone breast treatments or large full-
body immobilization.
Education and Innovation
In Research Question 2, it was demonstrated that the mean innovation
utilization score for MPs with a Master’s degree is higher than the mean
innovation utilization score for Doctoral degree (MD = 5.06, 95% CI[0.18,9.94],

106
t(188) = 2.046, p = 0.042, d = 0.278). Out of the 118 respondents with a Master’s
degree, 41.5% were employed by a center with a university affiliation, and 58.5%
of respondents were employed by a center without a university affiliation. Out of
the 72 respondents with a Doctoral degree, 58.3% were employed by a center
with a university affiliation, and 41.7% of respondents were employed by a center
without a university affiliation. The survey did not ask participants the topic of
their doctoral degree. It is possible that MPs with doctoral degrees in medical
physics are employed in university hospitals with higher innovation scores, while
MPs with doctoral degrees in other fields are employed in non-university
hospitals with lower innovation scores. This discrepancy does not exist for
Master’s degree, as the Master’s degree must be in Medical Physics to qualify for
certification. Even though the results are statistically significant, education is
likely to have a more complicated relationship with innovation. It is possible that
Masters level physicists are more motivated and competitive, but this requires
further study. This may partially explain the poor model fit in Research Question
2.
Appreciation and Motivation in Innovation
In Research Question 2, it was demonstrated that there is a small positive
correlation between innovation utilization and participant appreciation (rs = 0.224,
p = 0.002) and motivation (rs = 0.215, p = 0.003). Even though the correlations
were small, the results are in congruence with prior published studies in general
and in the health care setting (Wisdom et al., 2014). It is important to note that

107
this is the first time these parameters have been measured for MPs, and results are
in agreement with studies done on other health care professionals (Strömgren,
Eriksson, Bergman, & Dellve, 2016). Appreciation and motivation are often
considered “soft skills” that may be shunned by MPs in leadership positions
(Gutierrez, Halvorsen, & Rong, 2017). This common misconception is declining
since the introduction of the Medical Physics Leadership Academy and the 2016
summer school (J. Johnson, personal communication, July 14, 2019). The results
of this study will serve to strengthen the base of evidence supporting intra-
personal skills and clinical performance.
Barriers to Innovation Utilization
Four categories were found to have statistically significant barriers: patient
treatment, treatment planning, quality assurance, and workflow. Statistically
significant barriers were also detected for innovation utilization total. There were
no statistically significant barriers detected for patient positioning, possibly due to
lack of statistical power. Training and support was not a statistically significant
barrier for any of the categories investigated. This result is in agreement with the
AAPM TG 100 report listing training as the least effective tool of a quality
management program (Huq et al., 2016).
In the patient treatment category, lack of interest is a statistically
significant but with small effect size barrier in patient treatment innovation
utilization (rs = 0.199, p<0.05). It is noted that the patient treatment category
involved very advanced techniques, see Appendix D for details. This lack of

108
interest can be further explained in the context of university affiliation and
urbanicity. Interestingly, university centers in metropolitan areas had even higher
correlation coefficients for lack of interest in patient treatment innovation
utilization (results not shown). This finding may be an indicator of complacency
due to market domination (Martin et al., 2015; Roubou & Alexopoulou, 2015).
In the treatment planning category, five out of the seven barriers were
found to be statistically significant: lack of evidence (rs = 0.203, p<0.05),
complexity (rs = 0.175, p<0.05), lack of time and staffing (rs = 0.237, p<0.01),
lack of inter-operability (rs = 0.203, p<0.05), and lack of reimbursement (rs =
0.269, p<0.01). This is an alarming result; even though the coefficients are small,
there are multiple barriers. The highest coefficient, reimbursement, is the obvious
first choice for discussion. The treatment planning Current Procedural
Terminology (CPT) codes have been steadily decreasing, stagnant or bundled in
(“Reimbursement-American Society for Radiation Oncology (ASTRO)”, n.d.). In
health care in general, it has been well demonstrated that financial incentives
increase innovation utilization (Darzi & Parston, 2013). This conlusion is
congruent with the second-highest coefficient, lack of time and staffing resources.
In the absence of reimbursement, faced with low staffing support, the barrier to
innovation is significant. Facilities with mixed vendor products may face high
inter-operability issues, which are unfortunately unsolvable at the clinic level.
There is a growing number of publications on evidence for treatment planning
innovations and their effect on productivity and outcomes (Gintz et al., 2016;

109
Wang, Dong, Liu, & Xing, 2017), however, the results of this study show that
critical mass has not yet been reached. The complexity of treatment planning
innovations continues to be discouraging to users. These results may be of
particular interest to treatment planning vendors and to AAPM workgroups
writing recommendations for treatment planning.
In the quality assurance category, lack of time and staffing is a small
negative statistically significant barrier in quality assurance innovation utilization
(rs = -0.178, p<0.05). The negative relationship means that lower staffing levels
are correlated to higher innovation in quality assurance. This result can be
explained in the context of daily clinical work. It is reasonable to assume that
MPs have been forced into using innovations in quality assurance to compensate
for reduced staffing levels. For example, the first category indicator, portal
dosimetry, may take some initial time to set up, but the time gains for performing
device-less quality assurance for every patient multiple times per week is a
significant efficiency gain in the clinic. A similar concept applies to other
indicators in the quality assurance category (Eckhause et al., 2015; Thompson et
al., 2018). While it is positive that MPs are using quality assurance innovations,
the instigating factor may be convenience. This is in contrast with treatment
planning findings: when there is reduced staffing or time for treatment planning,
MPs do not use the innovations to gain time (for example with automatic planning
or automatic contouring) but instead do not use these innovations. This may be
due to the significant resource investment needed to create some of these

110
downstream benefits, and the involvement of other groups, such as dosimetrists
and radiation oncologists, who may not be positive towards these innovations
either (Georg & Thwaites, 2017). In contrast, physicists operate independently in
tasks in the quality assurance category.
In the workflow category, lack of inter-operability is a small statistically
significant barrier in workflow innovation utilization (rs = 0.218, p < 0.05). In the
context of workflow, inter-operability is not to be interpreted in a technical
context, but more as the compatibility of heterogeneous business processes. In
this frame of reference, MPs are encountering barriers in workflow innovations
when the innovations are perceived to be incompatible with existing policies and
procedures or standards of practice. This result is in agreement with prior results
in the Netherlands (M. Jacobs et al., 2017). It is possible that MPs have so far
been reluctant to get involved in process improvement and business development
planning. As previously discussed, these avenues are now being explored by the
AAPM and the Leadership Academy.
In total innovation utilization, there are multiple small statistically
significant barriers, such as lack of evidence (rs = 0.161, p < 0.05), lack of interest
(rs = 0.264, p<0.01), lack of inter-operability (rs = 0.214, p < 0.01), and lack of
reimbursement (rs = 0.176, p<0.05). The coefficients are small, yet statistically
significant. MPs face non-supportive organizational cultures in their clinics. This
is a key finding of this study. Clinics as organizational entities have selected to
reject innovations and maintain status quo, possibly due to the incorrect

111
association of innovations as a compromise to safety, the cornerstone of modern
RO.
Limitations of the Study
The presented study has limitations. Due to the study design, there was a
possible selection bias. The study may not have reached some MPs, especially
those who practice in rural areas. Since there are no known proportions of MPs
per ZIP code, the effect of this limitation is impossible to calculate. Comparison
with known proportions of university versus non-university centers showed a
reasonable degree of agreement, which implies that selection bias was not a
significant source of bias in this study. Another possible source of bias mentioned
in Chapter 1, information bias, could also have influenced the results.
Unfortunately, there is no way to assess the magnitude of this effect either. Both
of selection bias and information bias are inherent to the study design.
Additionally, as mentioned in Chapter 4, there was a high level of internal
consistency, as determined by Cronbach's alpha of 0.963. This statistic in
combination with the face and content validity of the expert panel review leads to
the conclusion that the constructs have high reliability. However, there were many
assumptions made in the operationalization of constructs. It is possible that not all
predictive parameters were included in the model, or operationalized
appropriately. This would partially explain the poor fit of the predictive model.
Additionally, the operationalization of constructs may not be transferable outside

112
the United States, thus results should be applied with caution outside of the
United States.
Furthermore, there are statistical limitations. The effect sizes used to
calculate a priori power were hypothetical and chosen conservatively. Post hoc
analysis for university status reveals that based on the detected sample effect size,
the power of the study was 0.72. This may be slightly smaller than the intended
0.8, yet still within reason. Conversely, the power for the RUCA continuum
ranged from 0.52 to 0.88, depending on the model selected. This is because of the
selected RUCA continuum and the low response rates from areas closer to the
rural end of the spectrum. It is uncertain if the effect sizes measured in this study
are true population effect sizes or sample effect sizes, thus results should be
interpreted with caution until effect sizes are confirmed by future studies.
Lastly, this was a cross-sectional study, thus the study design does not
allow the investigation of temporal relationships and possible causality between
the dependent and independent variables. Causal effects are typically
demonstrated by experimental study designs (Salazar et al., 2015). However, the
results are congruent with theoretical causal structures used in population health
(Darzi & Parston, 2013).
Recommendations
It is recommended that this study can be repeated in the future under the
aegis of the AAPM, possibly by a task group or workgroup. If so, the
questionnaire or survey should be designed to limit selection and information

113
bias, the two biggest limitations of this study. This could be achieved by
addressing the study to the department chair, manager, or chief physicist.
Changing the unit of measurement to the RO department, instead of the individual
MPs could also serve to minimize the aforementioned sources of bias. Even
without AAPM support, the results of this study should be validated by other
researchers. It would be particularly interesting to perform similar studies outside
the United States, assess generalizability and compare effect sizes.
Additionally, it is recommended that there is further theoretical
exploration on appreciation and motivation in health care leadership theory. There
is rich literature on emotional intelligence, organizational culture, and employee
motivation, but the connection to appreciation is not obvious. Very little has been
written about appreciation in the work environment. The Society for Human
Resource Management, (2012) claims that even though 51% of supervisors claim
they recognize good performance, only 17% of the same organization’s
employees feel recognized. The term “appreciative leadership” is often used in
popular management literature. Scholarly work does address appreciative
behaviors relating to praise and recognition, using verbiages such as support,
respect, constructive feedback, social reinforcement, and appreciation (Stocker,
Jacobshagen, Krings, Pfister, & Semmer, 2014). A possible expansion to the path-
goal theory of leadership (House, 1996), as it applies to healthcare, may be
necessary to fill this gap.

114
Another important aspect for further research is the transferability to
Radiation Therapy Technologists and Radiation Oncologists. These professionals,
along with MPs are in the front lines of daily clinical practice. The American
Society for Radiologic Technologists (ASRT) would be an obvious choice for
collaboration and dissemination of these findings. Similarly, collaborating with
Radiation Oncologists and ASTRO would be the logical route to further the
presented research and delve into qualitative and quantitative aspects of
organizational culture. MPs do not practice in isolation. It is possible that a better
predictive model could be derived using inter-team and intra-team dynamics
(Reiter-Palmon, 2017). Removing the barriers to innovation utilization in the
clinic must be a collaborative team effort.
Implications
Instrument Development and Benchmarking
During the literature review stage of this study, there was an evident
relationship between the ninth essential public health service to “evaluate
effectiveness, accessibility, and quality of personal and population-based health
services” and innovation accessibility in RO. There was no available data or an
instrument to effectively measure innovation in RO. This gap in itself is a barrier
to improving the equity of delivery of appropriate treatment to all cancer patients.
The need for a metric of innovation utilization was previously an abstract concept
discussed only in theory. This study has now delivered an instrument to quantify
innovation in RO. This quantitative instrument, along with qualitative work done

115
by others, will be used to improve innovation utilization in RO. The data collected
in this study can serve as a benchmark of the state of innovation today, with plans
on how to improve it in the future.
Social Change Implications
Inequalities in health are parallel to inequalities in health care (Frenk,
2013). To improve public health further in the 21st century, there needs to be an
inclusion of factors outside of traditionally-defined health care (DeSalvo, 2017).
Disparities in access to advanced care have an impact on cancer survival. This
statement may be considered contradictory by some, but it is well supported by
recent literature (Nardi et al., 2016; Pfister et al., 2015; Wolfson, Sun, Wyatt,
Hurria, & Bhatia, 2015). There are is an abundance of differences between centers
that may have a causal effect on improved cancer survival. Innovation is only one
of these parameters. This study did not attempt to show causal effects, as this can
only be demonstrated by clinical trials (B. L. Jacobs et al., 2017). What this study
did demonstrate, however, is that there are indeed differences in innovation
accessibility in RO in the United States. The connection between innovation and
improved cancer survival has been made by many authors; innovation-based care
models are under discussion in reimbursement health care reform (Alvarnas,
Majkowski, & Levine, 2015; Nardi et al., 2016). Thus, using the results of this
study to further how innovation is measured in RO in the United States, and
assess how the measured barriers can be minimized is a positive social change.
Public health is expanding beyond government agency programs to a broader

116
cross-sectoral practice (DeSalvo, 2017). RO as a community is in a position to
further engage public health aspects that have a collective impact on population
health.
Conclusion
In this study, innovation in RO in the United States was measured for the
first time, through the development of a new survey instrument. Rural centers and
centers with no academic affiliation are trailing behind in innovation
implementation. Motivation and appreciation were shown to be statistically
significant personal factors influencing innovation utilization, but no predictive
model was possible. Barriers in RO innovation implementation were also
assessed, with treatment planning showing the most statistically significant
barriers.
RO practitioners follow an ethos of “as low as reasonably achievable”
every day, making every attempt possible to reduce dose to patients. We do this
almost subconsciously, as it has been engrained in our training as common sense.
Getting MPs to view embracing innovation as part of their culture will only be
possible if innovation is not considered to be competing with safety. The
complementary relationship between safety and innovation is being discussed in
many other health care fields. If every MPs practiced using “as innovative as
reasonably achievable” as their mantra, similar to “as low as reasonably
achievable”, patients would benefit immensely. This is a worthy end goal to be
striving towards. This study provides a small but promising step in this direction.

117
Although the exact number of lives saved or extended because of innovations in
daily practices in RO may never be known, it is certainly worth it to try to make
every treatment as innovative as reasonably achievable.

