



1
Chapter 1
Introduction
BACKGROUND
The relationships between economic indicators and health have been a subject of research
for the last two decades in the United States (US) (1-12). Economic, epidemiological and
sociological studies have been conducted to examine the direction of this relationship and
determine the possible causal pathways (1-12). Mortality rates are the gold standard for
measuring health status. However, mortality is an absorbing event, and cannot be used to
examine the way that health changes over the life cycle (13). Therefore, prior studies used
metrics other than mortality to analyze the link between economic indicators and health.
Numerous studies have indicated that economic indicators (i.e. family income, labor income, net
wealth) are positively associated with various physical health measures (e.g.: self-rated health)
(1,4-6,14-18) and negatively with mental health measure (psychological distress and disorders)
(9,11,12) Nevertheless, the consensus on the magnitude of the relationships lacks among those
studies. Further, some studies revealed no associations between economic indicators and some
physical and mental health measures (7,8,11).
The inconsistent findings may be attributed to four challenges to evaluating the
relationships between economic indicators and health: 1) heterogeneity in measures of health; 2)
heterogeneity in measures of economic indicators; 3) endogeneity between economic indicators
and health due to reverse causality and unobserved heterogeneity; and (4) lack of comprehensive
adjustors such as race/ethnicity, sex, and other risk factors that may affect health (example:
smoking, alcohol use, physical activity and obesity).

2
Physical and Mental Health Measures
World Health Organization defines health as “a state of complete physical, social and
mental well-being, and not merely the absence of disease or infirmity (19).” Therefore, health is
a complex multidimensional concept, and is dependent on the interactions between physical,
mental, and social dimensions. Although health is not only the absence of diseases, presence of
diseases can affect various dimensions of health. For example, the presence of a high disabling
disease like arthritis can affect physical, mental, and social dimensions of health. It should be
noted that there is no single measure that captures all the dimensions of health (20). Also, it is
difficult to measure all health aspects simultaneously. Therefore, the current dissertation focuses
on physical and mental dimensions of health.
Physical Health
There is a wide variation in how physical health is measured. Some studies have used
self-rated health (2,4,6,7,14,21-24), presence of chronic conditions (1,5,7,14,16,25-27) and
functional limitations due to chronic conditions (16) to represent physical health. These measures
are often chosen because they are highly correlated with mortality (28), productivity loss (29,30),
and are easy to obtain (28,31). Descriptions of physical health measure are as follow:
Self-rated Health
Self-rated health (SRH) is a widely used measure of physical health in epidemiological,
medical and economic research (32-35). It is based on asking individuals to rate their health
status on a five-point scale (Excellent, very good, good, fair, and poor) (32-35). SRH is a reliable
and valid measure of health (32-35). SRH can be used independently as a predictor of mortality.
In fact, previous studies suggested a consistent association between poor self-ratings of health

3
and higher risk of mortality (28). Additionally, SRH is significantly associated with morbidity
(36,37). SRH also provides broad measure of individuals’ health that goes beyond morbidity and
mortality (38). In 2014, 11.9% of US adults (≥18 years) reported their health as fair or poor (39).
In the US, SRH varies by poverty status, as 26.8 % of poor adults reported their health as fair or
poor while 7.4% of not poor adults reported their health as fair or poor (39). Therefore, this
measure of health has been widely used in assessing the relationships between economic
indicators and health. Some studies have reported positive associations between economic
indicators (family income, labor income and net wealth) and SRH (4-6,15,40). However, one
study revealed no relationship (7) between net wealth and SRH.
Chronic Conditions-Attributable Functional Limitations
Chronic conditions prevalence has increased dramatically in the US (41). In 2012, 117
million (1 in 2) adults lived with at least one chronic condition from a list of selected ten
conditions (hypertension, coronary heart disease, stroke, diabetes, cancer, arthritis, hepatitis,
weak or failing kidneys, current asthma, or chronic obstructive pulmonary disease) (41).
Although WHO definition of health states that the absence of a disease does not equal perfect
health, presence of a chronic condition imposes a threat to multiple dimensions of health.
Chronic conditions are highly associated with psychological disorders such as depression and
psychological distress (42,43). Also, disabling chronic conditions can minimize the functioning
of working-age and elderly adults (44). In 2014, 12.2% of US adults who aged 18 or over had
limitation(s) in their abilities to engage in work, social, and daily living activities due to one or
more chronic conditions (44). Furthermore, chronic conditions are highly associated with
productivity losses and lost in income (45,46). The studies have found that adults with lower

4
income and wealth have higher number of chronic conditions and higher limitations due to
chronic conditions (5,16,17).
Mental Health
Mental health is “a state of well-being in which every individual realizes his or her own
potential, can cope with the normal stresses of life, can work productively and fruitfully, and is
able to make a contribution to her or his community (47).” Mental health is an important
dimension of an individual’s health, and there is a paucity of research on the relationship
between economic indicators and mental health. In the US, 43.6 million US adults (18.1%)
experienced poor mental health due to the presence of mental health conditions (48) such as
anxiety, depression, and bipolar disorders (48). Poor mental health is profoundly disabling (49)
and costly to the society and the patients and their families (50). For example, depression is the
second leading cause of disability (49); both depression and anxiety were associated with high
financial burden to the payors/patients and/or their families (51), productivity loss (52), and
healthcare expenditures (50). Studies have reported that psychological disorders and stress are
correlated with low-income (9,11,43,53-56). Although numerous studies have evaluated the
relationship between changes in mental health and the probability of employment (57-62), only a
handful of studies has examined the link between economic indicators and mental health
(9,11,12,53). These studies have documented inverse associations between economic indicators
and psychological distress and disorders (9,11,12,53). Nonetheless, those studies did not relate
the change in the economic indicators to the change in health. Therefore, the studies on the
dynamic relationship between economic indicators and health are limited.

5
Economic Indicators
It has been considerable debate over the best economic indicator that represents
individuals’ economic status. Household income, net wealth, home ownership, earnings and
wages from employment, poverty, and household expenditures are all measures that have been
used in the research to represent individuals’ economic well-being. Income reflects a temporary
flow of financial resources at one time-point and is considered more responsive to changes in
health. As a result, many studies have used household, family or labor income
(4,15,16,18,22,25,26,63) to represent the economic well-being of an individual. On the other
hand, wealth is the accumulated financial resources over the lifetime of an individual (64,65) and
considered more stable than income. As individuals and families can rely on accumulated wealth
in times of unemployment or times of declining health, some studies used wealth to examine the
relationships between economic indicators and health (5,6). However, health is a
multidimensional concept and economic indicators seem to have different dynamic relationships
with different components of health (4-7,22,23).
Endogeneity between Economic Indicators and Health
The relationship between economic indicators and health may be reciprocal. From
economic point of view, individuals with good health may have higher financial resources
compared to those with poor health because they can participate in activities that generate
income (22,66,67). From epidemiology and health policy perspectives, individuals with higher
financial resources have better health because they have better access to healthcare through
health insurance or able to spend out-of-pocket on healthcare (22,67,68). It is important to
address the endogeneity due to reverse causality between economic indicators and health in the
analyses to compute consistent unbiased estimates. Previous studies have employed some

6
statistical techniques including instrumental variables to address the endogeneity. However, it is
difficult to find a valid instrument that is strongly correlated with economic indicators and has no
direct effect on health. Therefore, future research needs to employ statistical techniques that
address the endogeneity between economic indicators and health without using weak
instruments.
Factors affect economic indicators, health or both
Many factors can alter the relationships between economic indicators and health
including age, sex, race/ethnicity and others. For example, the relationships between economic
indicators and health may vary by age groups as a result of the differences between working-age
and elderly adults (69-71). To capture the actual magnitude of the relationships between
economic indicators and health, researchers need to examine the relationships between the two
within working-age and elderly adults separately. Elderly adults have different economic
resources as compared to working-age adults (69-71). Elderly adults may have no labor income
because they are less likely to be employed. Another factor is the type of health insurance.
Working-age adults usually get their health insurance through their work or they buy private
health insurance (72). Conversely, elderly adults are eligible for public health insurance through
the government (73). Furthermore, elderly adults have higher health care needs due to the natural
process of aging. All these factors may alter the relationships between economic indicators and
health, and it is expected that the magnitude of the relationships would be different between
these two age groups. The appropriate economic indicators and health measures also vary by
these two age groups (1-12). Further, it is crucial to control for other factors that can affect
economic indicators or health such as marital status, physical activity, alcohol use, region of
residence, metro status, and others.

7
Studies on the racial/ethnic disparities in the relationships between economic indicators
are sparse. Racial and ethnic minorities have poorer health and less wealth as compared to the
white individuals (74,75). From 1984 to 2007, the wealth gap increased more than four times
between whites and African Americans (74). Also, African Americans and Hispanics have
higher mortality rates as compared to their white counterparts (75). Few studies have highlighted
the differences in the relationship between racial minorities and white individuals (11,16,76,77).
Nonetheless, most of these studies have utilized cross-sectional samples and all of them suffer
from the limitations mentioned above.
NEED FOR THE STUDY
Prior studies have suggested positive or no relationships between economic indicators
and health (1-12). While these studies have made significant contributions in this area, a
comprehensive evaluation of the relationships between economic indicators and health is still
lacking. Most studies have used a single measure of health (1-12); the concept of health is
abstract, and no single measure can capture all health dimensions (20). Of special interest is the
relationship between economic indicators and mental health, specifically psychological distress,
depression and/or anxiety because of the heavy illness burden (49). Yet, there are only a few
studies in this area (9,11,12,53). Further, most studies have focused on one-direction – economic
indicators affecting health; little is known about the effect of health improvement on gain in
economic status. Moreover, given the long-history of racial discrimination, differential effect of
poverty on health between whites and African Americans, racial inequities in education and
healthcare resources (74,78,79), it is important to examine racial disparities in the relationship
between economic indicators and health. Only a few studies have conducted comparative
analysis of whites and racial minorities (11,16,76,77). Furthermore, previous studies have not

8
adequately controlled for endogeneity between economic indicators and health due to reverse
causality, omitted variables and unobserved heterogeneity (2,4-6,9,11,12,40).
Understanding the relationship between economic indicators and health is crucial to suite
policies and programs. If there is a strong positive relationship between economic indicators and
health, policy makers need to focus on upstream factors (i.e. economic status) rather than
healthcare behavior and services. In addition, any sex or racial disparities in the link between
economic indicators and health will inform the policy makers on the need for special programs
for the minorities in US. Such programs need to address the racial economic inequality to
attenuate the racial health disparities in US.
The present dissertation addressed many of the limitations of existing studies by (1) using
a variety of health measures and economic indicators; (2) modeling dynamic rather than static
relationship between economic indicators and health; (3) adjusting for endogeneity that is caused
by unobserved heterogeneity, measurement error and reverse causality by using novel statistical
techniques; (4) and using a nationally representative database with the ability to track individuals
over time.
AIMS, OBJECTIVES AND HYPOTHESES
AIM 1: Examine the dynamic relationships between economic status (family income, labor
income and net wealth) and physical health measures (self-rated health and functional limitations
due to chronic conditions) among working-age adults in the US.
Hypothesis 1.1: A decrease in economic indicators will lead to a decline in health; improvements
in health will lead to increases in economic indicators.

9
AIM 2: Evaluate the dynamic relationships between economic indicators (family income, labor
income and net wealth) and mental health (psychological distress and mental illnesses) among
working-age adults in the US.
Hypothesis 2.1: A decrease in economic indicators will lead to a decline in mental health;
improvements in mental health will lead to increases in economic indicators.
AIM 3: Evaluate the heterogeneous relationships between labor income and physical and mental
health by racial groups.
Hypothesis 3.1: Whites and African Americans with higher labor income will have better
physical health.
Hypothesis 3.2: Whites who experience a decline in labor income will also experience a decline
in physical and mental health.
Hypothesis 3.3: There will not be a statistically significant relationship between labor income
and mental health among African Americans and Hispanics.
CONCEPTUAL FRAMEWORK
The present dissertation was guided by a simple health economics framework in which
health capital, human capital and financial capital interact with each other. From a health
economic perspective, an individual born with a fixed health capital stock (health capital), which
declines with age because of biological processes (13). Michael Grossman (80) posits that
education (human capital) increases the efficient use of medical care and educated individuals
are more likely to improve their healthcare or effectively address/reverse a health decline.
Therefore, education rather than income or wealth is the primary driver of health. Case and
Deaton (13) improved on Michael Grossman’s framework and suggested that the link between
health and economic indicators are affected not only by health capital and human capital, but
10
also the financial resources an individual has (financial capital). The model further assumes that
there is equitable distribution of health at time of birth and this is not the case with human and
financial capital. Individuals with less human and financial capital, rely heavily on their health
capital and health capital deteriorates faster. Therefore, poor and less educated individuals are
more likely to have poor health. This was further expanded by Galama (66) who used health
capital as the foundation and suggested that health may also affect economic indicators. Under
his framework, “unhealthy individuals drop out of the labor force sooner, and lose income as a
result”. Although Case and Deaton acknowledge that other factors may affect both health and
financial capital, these factors were operationalized by Strauss and Thomas (81).
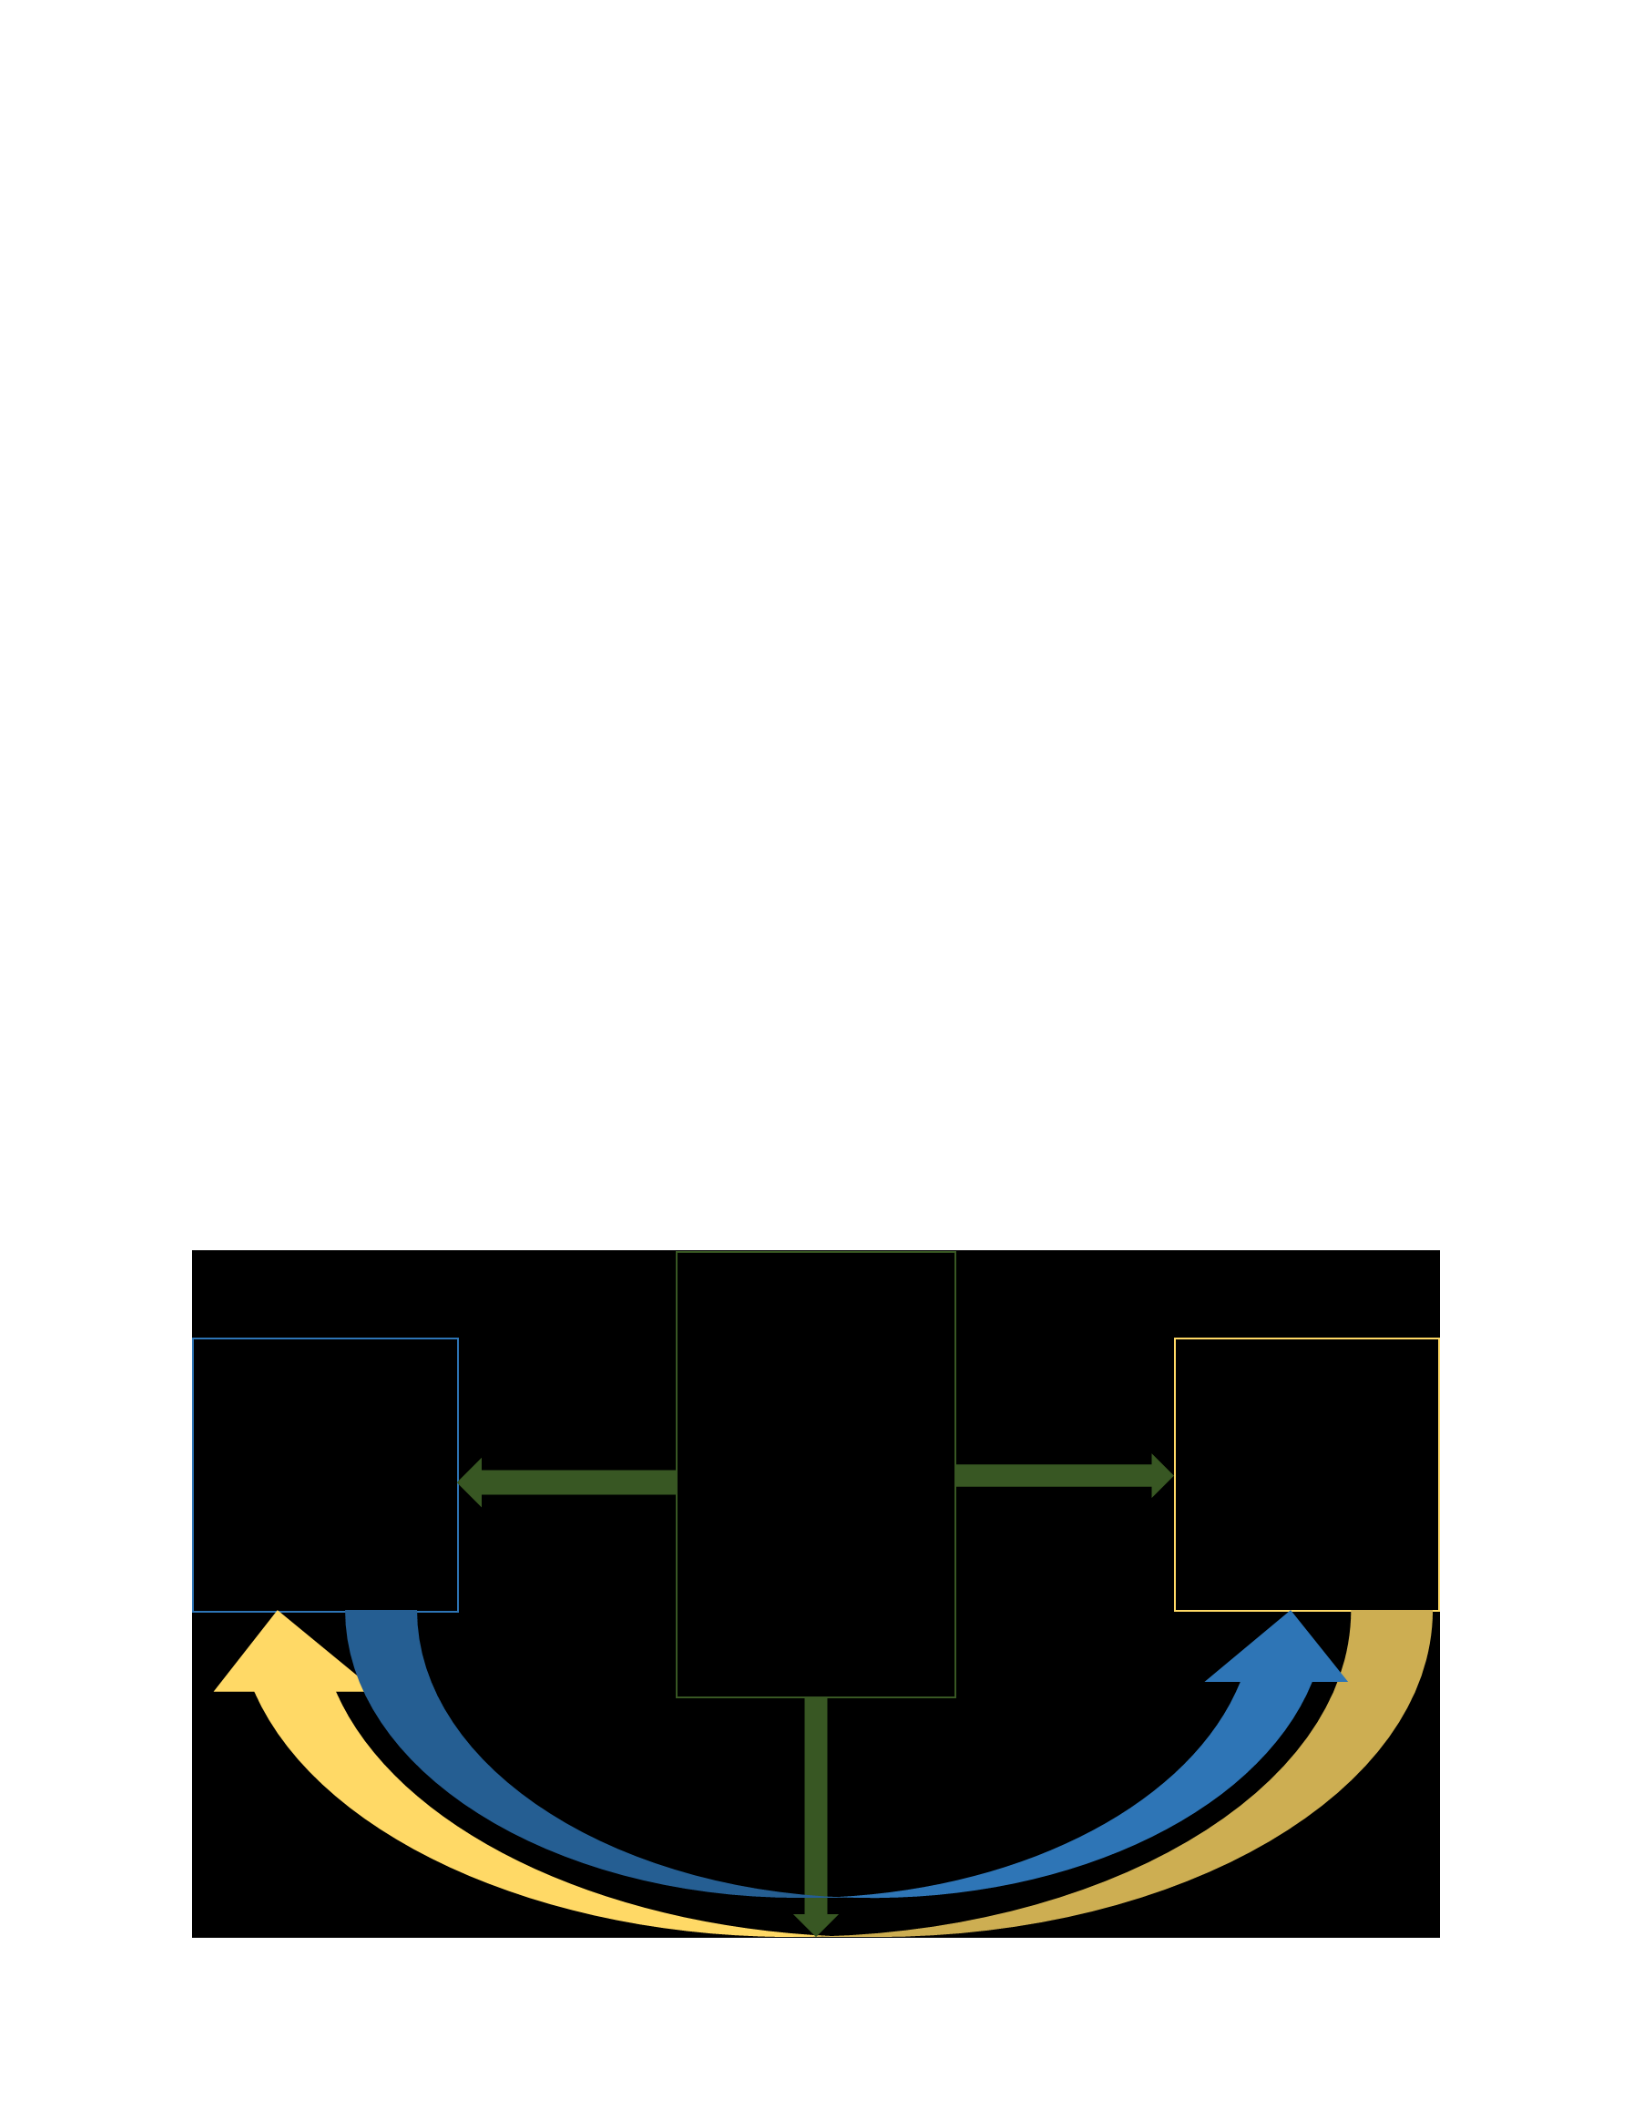
In this dissertation, we have integrated the frameworks and suggest that lower economic
well-being leads to health decline and subsequent improvement in health can lead to higher
economic well-being while adjusting for other factors that affect both economic indicators and
health (Figure 1.1).
Figure 1.1: The Bidirectional Relationship between Economic Status and Health

11
DATA SOURCES
Information from the Panel study of Income Dynamics was utilized in all specific aims.
Information on metros’ level of unemployment rate was retrieved from The Area Health
Resource File, and was linked to the PSID at the state and metro level.
The Panel Study of Income Dynamics (PSID)
The PSID was created in 1966 to assess President Lyndon Johnson’s War on Poverty
(82,83). The original PSID 1968 sample was drawn from two independent samples: an over-
sample of 1,872 low-income families from the Survey of Economic Opportunity; and a
nationally representative sample of 2,930 families (82,83). Those two samples constituted a
national probability sample of U.S. families in 1968 (82,83). The PSID further follow these
families and others to maintain a representative sample at any point in time and across time. The
PSID included all Individuals in the 1968 families and new-born or adopted Individuals (82,83).
The PSID also follow Individuals in 1968 families who started new families (82,83). In the
PSID, individuals in 1968 families are called “sample individuals”. Those sample individuals
and their descendants are followed for their lifetime. In addition, non-sample individuals are
followed if they marry sample individuals as long as they stay in the sample individual family
unit. The PSID has achieved high response rates (e.g.: 94.7% in 2009) (82,83). Households were
interviewed annually between 1968 and 1997, and biannually since then. As of 2015, 39 waves
of PSID have been collected, and 25,000 individuals in 10,000 families have been interviewed
(82-84).
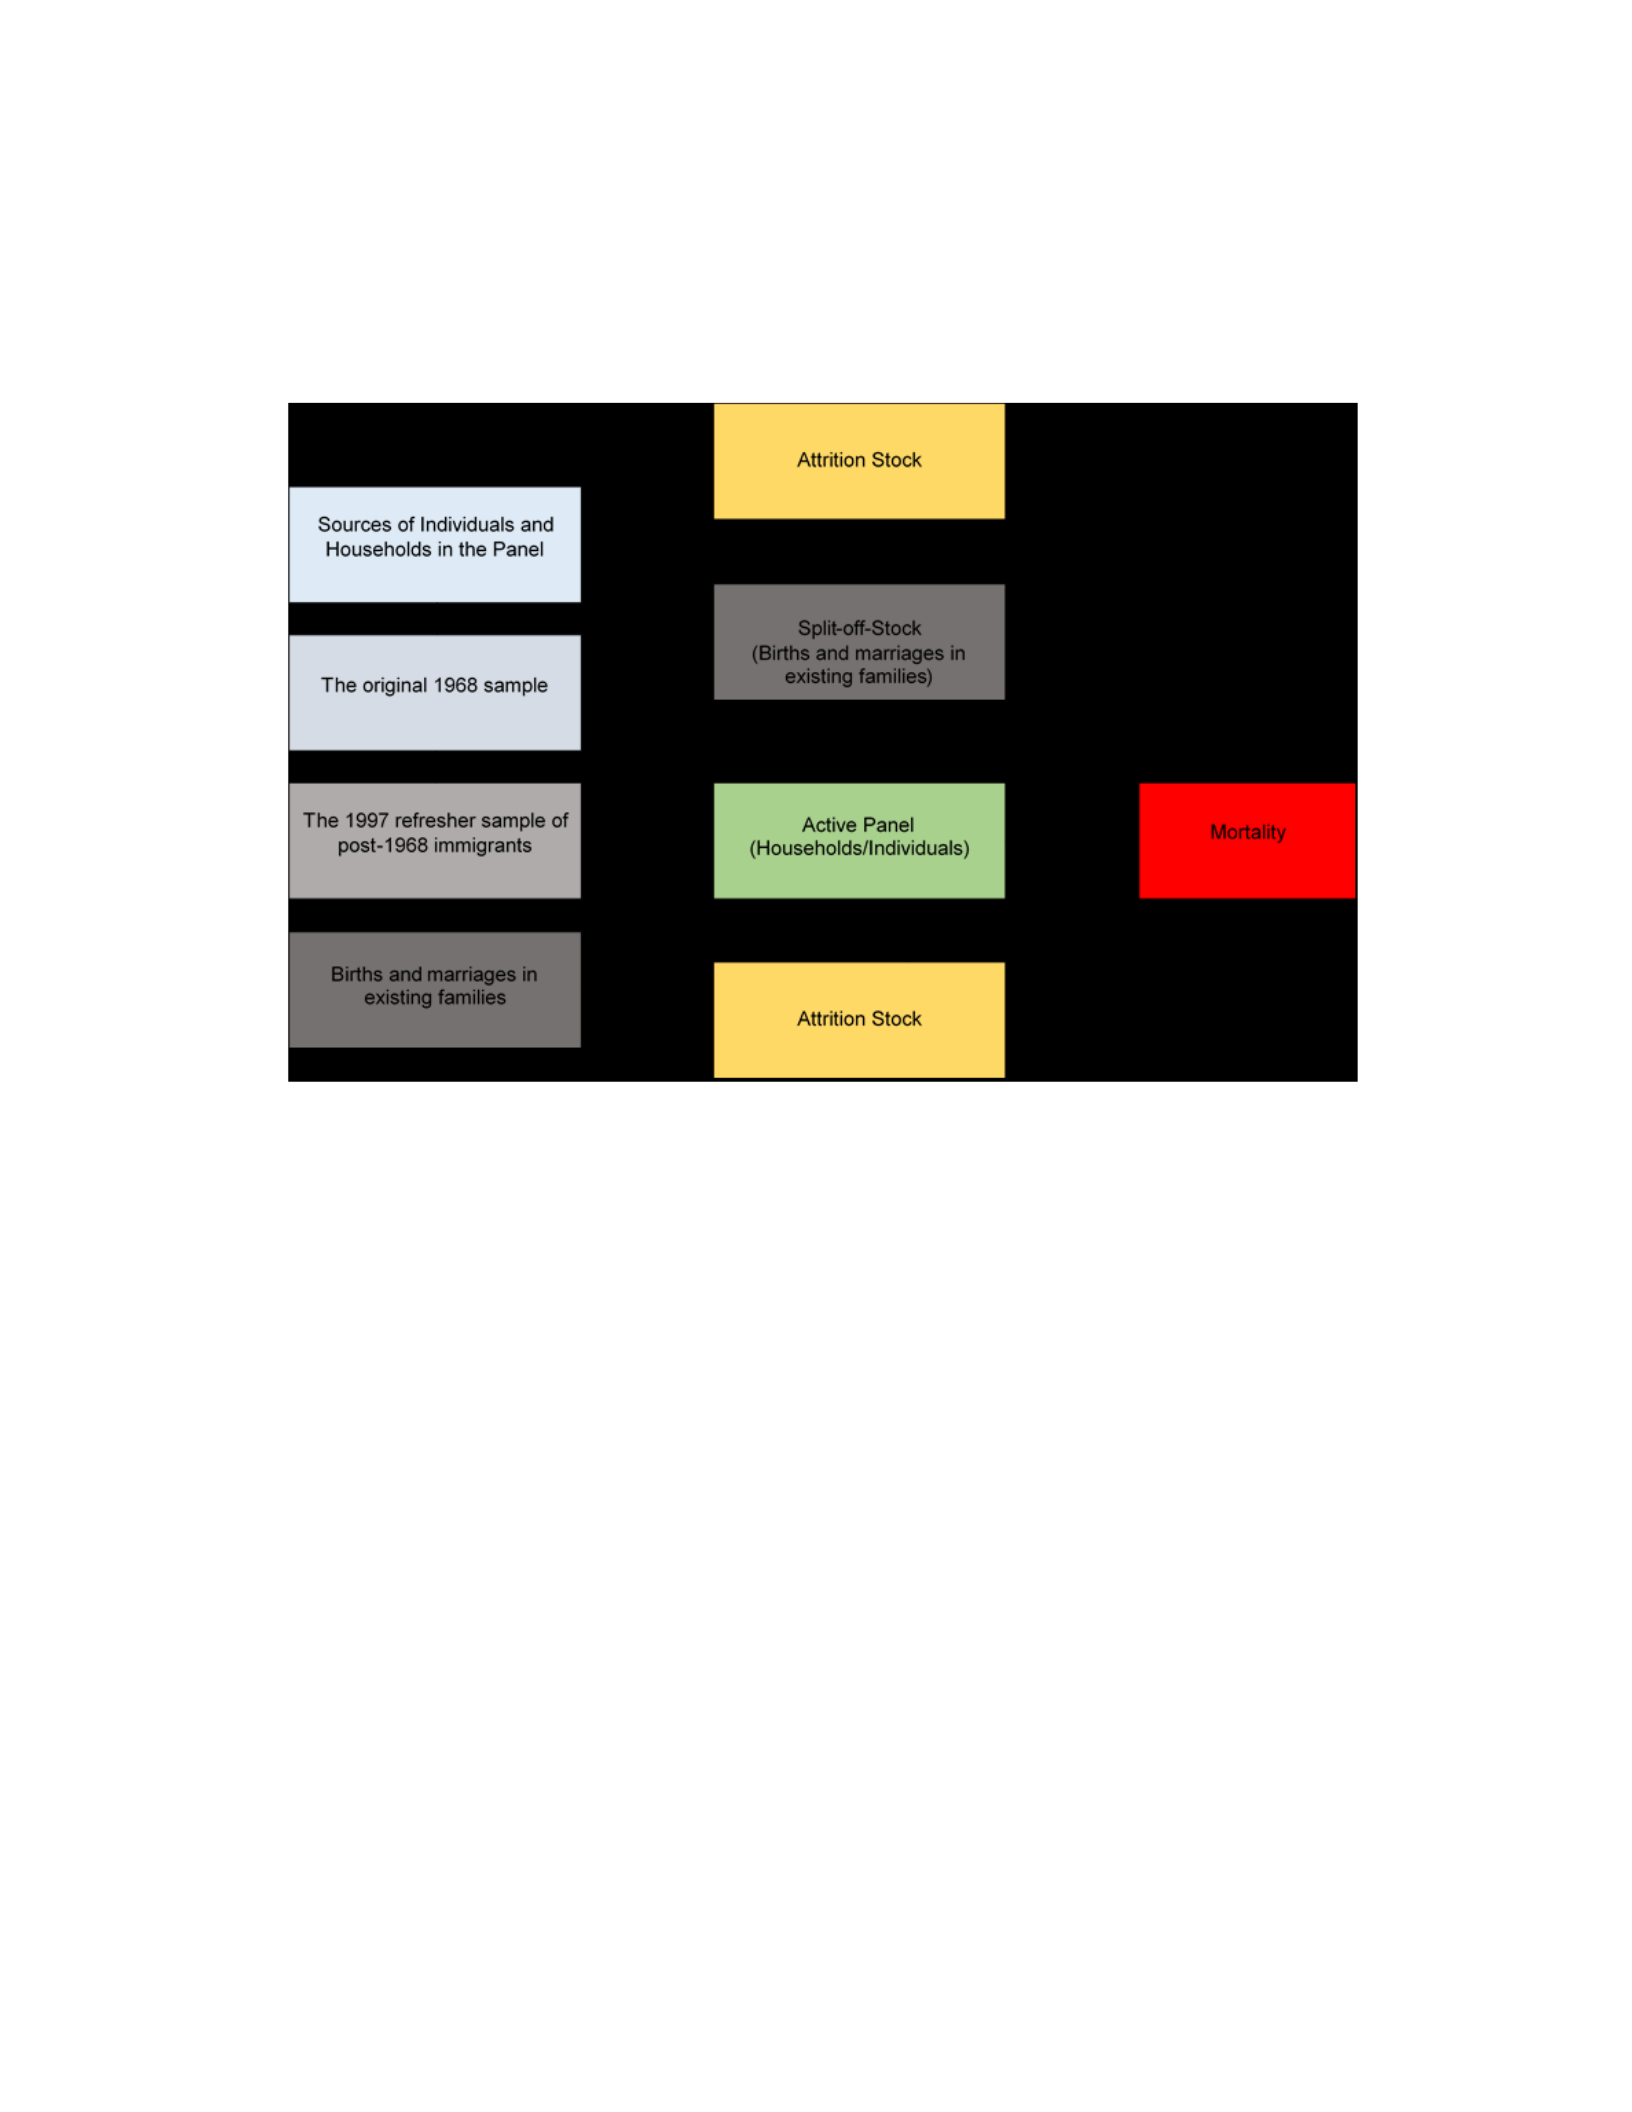
Currently, the individuals in any panel come from three sources: the original 1968
sample; the 1997 refresher sample of post 1968 immigrants; and births and marriages in existing
12
families (82-84). PSID is the only data set that provides information on life course and
multigenerational economic conditions, well-being, and health (82-84).
Figure 1.2: Steady State Panel Schematic
Interview data are released with five different files: family file, cross-year individual file,
birth history file, marriage history file, and parent identification file (84). In this dissertation,
both family and cross-year individual files, which are publicly available, will be used to gather
information on households. Most of the information about households’ heads and their wives are
available in the family file. Information on demographic, education, family composition, health
behavior, health care utilization, health history, health insurance, health status, economic
indicators are all available in the family file (84). On the contrary, limited information on every
person who was ever in an interviewed family at any point is available in the cross-year
individual file. It should be noted that the PSID provides other supplemental studies including
child development supplement, transition into adulthood supplement, disability and use of time,
and intergenerational transfer (84). For the purpose of the current study, we restricted our

13
analyses to the households’ heads who were continuously in the panel between 1999 and 2013.
Figures 1.2 and 1.3 depict the panel design of PSID.
Figure 1.3: Split-Offs Family Units
The Area Health Resource File (AHRF)
Unemployment rates were derived from the AHRF, provided by the Department of
Health and Human Services (85). This information was linked to the PSID by using five-digit
Federal Information Processing Standard (FIPS) codes at the metro-level.

14
REFERENCES
(1) Fiscella K, Franks P. Individual income, income inequality, health, and mortality: what are
the relationships? Health services research 2000;35(1 pt2):307-318.
(2) McDonough P, Berglund P.. Histories of poverty and self-rated health trajectories. Journal of
Health and Social Behavior 2003;44(2):198-214.
(3) Meer J, Miller DL, Rosen HS. Exploring the health–wealth nexus. . Journal of health
economics 2003;22(5):713-730.
(4) Berry B. Does money buy better health? Unpacking the income to health association after
midlife. Health(London) 2007;11(2):199-226.
(5) Hajat A, Kaufman JS, Rose KM, Siddiqi A, Thomas JC. Do the wealthy have a health
advantage? Cardiovascular disease risk factors and wealth. Social Science and Medicine
2010;71(11):1935-1942.
(6) Hajat A, Kaufman JS, Rose KM, Siddiqi A, Thomas JC. Long-term effects of wealth on
mortality and self-rated health status. American Journal of Epidemiology 2011;173(2):192-200.
(7) Michaud PC, van Soest A. Health and wealth of elderly couples: causality tests using
dynamic panel data models. Journal of Health Economics 2008;27(5):1312-1325.
(8) Halliday TJ. Earnings Growth and Movements in Self-Reported Health. Review of Income
and Wealth 2016.
(9) Sareen J, Afifi TO, McMillan KA, Asmundson GJ. Relationship between household income
and mental disorders: findings from a population-based longitudinal study. Archives of General
Psychiatry 2011;68(4):419-427.
(10) Lorant V, Deliège D, Eaton W, Robert A, Philippot P, Ansseau M. Socioeconomic
inequalities in depression: a meta-analysis. American Journal of Epidemiology 2003;157(2):98-
112.
(11) McMillan KA, Enns MW, Asmundson GJ, Sareen J. The association between income and
distress, mental disorders, and suicidal ideation and attempts: findings from the collaborative
psychiatric epidemiology surveys. . The Journal of clinical psychiatry 2010;71(9):1168-1175.
(12) Yilmazer T, Babiarz P, Liu F. The impact of diminished housing wealth on health in the
United States: Evidence from the Great Recession. Social science & medicine 2015;130:234-
241.
(13) Case A, Deaton A. Broken down by work and sex: How our health declines. Analyses in the
Economics of Aging, University of Chicago Press. 2005:185-212.
(14) Adams P, Hurd MD, McFadden DL, Merrill A, Ribeiro T. Healthy, wealthy, and wise?
Tests for direct causal paths between health and socioeconomic status. Journal of Econometrics
2003;112(1):3-56.

15
(15) Robert SA, Cherepanov D, Palta M, Dunham NC, Feeny D, Fryback DG. Socioeconomic
status and age variations in health-related quality of life: Results from the national health
measurement study. Journal of Gerontology: Social Sciences 2009;64B(3):378-389.
(16) Braveman PA, Cubbin C, Egerter S, Williams DR, Pamuk E. Socioeconomic disparities in
health in the United States: what the patterns tell us. American journal of public health
2010;100(S1):S186-S196.
(17) Do DP, Frank R, Finch BK. Does SES explain more of the black/white health gap than we
thought? Revisiting our approach toward understanding racial disparities in health. Social
science & medicine 2012;74(9):1385-1393.
(18) Golberstein E. The effects of income on mental health: evidence from the social security
notch. The journal of mental health policy and economics 2015;18(1):27-37.
(19) Preamble to the Constitution of the World Health Organization as adopted by the
International Health Conference. ; 1948.
(20) Turnock B J. Chapter 2: Understanding and Measuring Health. Public Health: what it is and
how it works turnock. 6th ed. Burlington, MA, USA: Jones & Bartlett Publishers; 2011. p. 21-47.
(21) Kennedy BP, Kawachi I, Glass R, Prothrow-Stith D. Income distribution, socioeconomic
status, and self rated health in the United States: multilevel analysis. BMJ 1998;317(7163):917-
921.
(22) Halliday T. Income volatility and health. Discussion Paper No 3234, IZA 2007.
(23) Halliday T. Earnings Growth and Movements in Self-Reported Health. IZA 2012;6367:1-
51.
(24) Meyer OL, Castro-Schilo L, Aguilar-Gaxiola S. Determinants of mental health and self-
rated health: a model of socioeconomic status, neighborhood safety, and physical activity. .
American journal of public health 2014;104(9):1734-1741.
(25) Banks J, Marmot M, Oldfield Z, Smith JP. Disease and disadvantage in the United States
and in England. JAMA 2006;295(17):2037-2045.
(26) Chung Y. Chronic Health Conditions and Economic Outcomes. Unpublished mimeo 2013
http://www.sole-jole.org/14225.pdf.
(27) Grafova IB. Financial status and chronic conditions onset among non-elderly adults. Review
of Economics of the Household 2015;13(1):53-72.
(28) Idler EL BY. Self-rated health and mortality: a review of twenty-seven community studies.
Journal of Health and Social Behavior 1997;38(1):21-37.
(29) Alecxih L, Shen S, Chan I, Taylor D, Drabek J. Individuals Living in the Community with
Chronic Conditions and Functional Limitations: A Closer Look. 2010.
(30) Anesetti-Rothermel A SU. Physical and mental illness burden: disability days among
working adults. Population health management 2011;14(5):223-230.

16
(31) Xu JQ, Murphy SL, Kochanek KD, Bastian BA. Deaths: Final data for 2013. National vital
statistics reports. National Center for Health Statistics 2016;64(2).
(32) Zajacova A DJ. Reliability of self-rated health in US adults. American Journal of
Epidemiology 2011;174(8):977-983.
(33) Bombak AE. Self-Rated Health and Public Health: A Critical Perspective. Front Public
Health 2013;1(15).
(34) Allore HG, Zhan Y, Tinetti M, Trentalange M, McAvay G. Longitudinal average
attributable fraction as a method for studying time-varying conditions and treatments on
recurrent self-rated health: the case of medications in older adults with multiple chronic
conditions. Annals of epidemiology 2015;25(9):681-686.
(35) Hays RD, Spritzer KL, Thompson WW, Cella D. US general population estimate for
“excellent” to “poor” self-rated health item. Journal of general internal medicine
2015;30(10):1511-1516.
(36) Chamberlain AM, Manemann SM, Dunlay SM, Spertus JA, Moser DK, Berardi C, Kane
RL, Weston SA, Redfield MM, Roger VL. Self-rated health predicts healthcare utilization in
heart failure. Journal of the American Heart Association 2014;3(3):1-8.
(37) Wagner DC. Longitudinal predictors of self-rated health and mortality in older adults.
Preventing chronic disease 2014.
(38) Zack MM, Moriarty DG, Stroup DF, Ford ES, Mokdad AH. Worsening trends in adult
health-related quality of life and self-rated health-United States, 1993-2001. Public health reports
2004;119(5):493-505.
(39) Blackwell DL LJ. Tables of Summary Health Statistics for U.S. Adults: 2014 National
Health Interview Survey. 2015.
(40) Franks P, Gold MR, Fiscella K. Sociodemographics, self-rated health, and mortality in the
US. Social science & medicine 2003;56(12):2505-2514.
(41) Ward BW. Multiple chronic conditions and labor force outcomes: A population study of
U.S. adults. American Journal of Industrial Medicine 2015;58(9):943-954.
(42) Egede LE, Zheng D, Simpson K. Comorbid depression is associated with increased health
care use and expenditures in individuals with diabetes. Diabetes Care 2002 Mar;25(3):464-470.
(43) Weissman J, Pratt LA, Miller EA, Parker JD. Serious psychological distress among adults:
United States, 2009–2013. National Center for Health Statistics 2015;NCHS data brief(203).
(44) Adams PF BV. Tables of Summary Health Statistics for the U.S. Population: 2014 National
Health Interview Survey. . 2015.
(45) DeVol R BA. An unhealthy America: The economic burden of chronic disease--charting a
new course to save lives and increase productivity and economic growth. 2007.

17
(46) Vuong TD, Wei F, Beverly CJ. Absenteeism due to Functional Limitations Caused by
Seven Common Chronic Diseases in US Workers. . Journal of Occupational and Environmental
Medicine 2015;57(7):779-784.
(47) Herman H, Saxena S, Moodie R. Promoting Mental Health: Concepts, Emerging Evidence,
Practice. Geneva, Switzerland: World Health Organization; 2005.
(48) Center for Behavioral Health Statistics and Quality. Behavioral health trends in the United
States: Results from the 2014 National Survey on Drug Use and Health. Available at:
http://www.samhsa.gov/data/. Accessed 07/22, 2016.
(49) Murray CJ, Abraham J, Ali MK, Alvarado M, Atkinson C, Baddour LM, Bartels DH,
Benjamin EJ, Bhalla K, Birbeck G, Bolliger I. The state of US health, 1990-2010: burden of
diseases, injuries, and risk factors. JAMA 2013;310(6):591-606.
(50) Levit KR, Kassed CA, Coffey RM, Mark TL, McKusick DR, King E, Vandivort R, Buck J,
Ryan K, Stranges E. Projections of National Expenditures for Mental Health Services and
Substance Abuse Treatment, 2004¬– 2014¬. SAMHSA 2008;SMA 08-4¬326.
(51) Greenberg PE, Fournier AA, Sisitsky T, Pike CT, Kessler RC. The economic burden of
adults with major depressive disorder in the United States (2005 and 2010). The Journal of
clinical psychiatry 2015;76(2):155-162.
(52) Stewart WF, Ricci JA, Chee E, Hahn SR, Morganstein D. Cost of lost productive work time
among US workers with depression. JAMA 2003;289(23):3135-3144.
(53) Prause J, Dooley D, Huh J. Income volatility and psychological depression. . American
Journal of Community Psychology 2009;43(1-2):57-70.
(54) Messias E, Eaton WW, Grooms AN. Income inequality and depression prevalence across
the United States: an ecological study. Psychiatric Services 2011;62(7):710-712.
(55) Bogan VL FA. Portfolio choice and mental health. Review of Finance 2013;17(3):955-992.
(56) Pabayo R, Kawachi I, Gilman SE. Income inequality among American states and the
incidence of major depression. Journal of epidemiology and community health 2013;jech-
2013:1-6.
(57) Ettner, S., R. Frank, and R. Kessler. The Impact of Psychiatric Disorders on Labor Market
Outcomes. Industrial and Labor Relations Review 2007;51(1):64-81.
(58) Dooley, D., J. Prause, and K.A. Ham-Rowbottom. Underemployment and Depression:
Longitudinal Relationships. Journal of Health Social Behavior 2000;41(4):421-436.
(59) Chatterji, P., M. Alegria, M. Lu, and D. Takeuchi. Psychiatric Disorders and Labor Market
Outcomes: Evidence from the National Latino and Asian American Study. Health Economics
2007;16(10):1069-1090.
(60) Chatterji, P., M. Alegria, and D. Takeuchi. Psychiatric Disorders and Labor Market
Outcomes: Evidence from the National Comorbidity Survey-Replication. Journal of Health
Economics 2011;30(5):858-868.

18
(61) Baldwin, M., and S. Marcus. The impact of mental and substance-use disorders on
employment transitions. Health Economics 2014;23(3):332-344.
(62) Mitra S JK. The impact of recent mental health changes on employment: new evidence from
longitudinal data. Applied Economics 2016:1-4.
(63) Duncan GJ, Daly MC, McDonough P, Williams DR. Optimal indicators of socioeconomic
status for health research. American Journal of Public Health 2002;92(7):1151-1157.
(64) Keister LA. Wealth in America: Trends in wealth inequality. Cambridge, UK: Press
Syndicate of the University of Cambridge.; 2000.
(65) Shapiro TM, & Wolff EN. Assets for the poor: The benefits of spreading asset ownership.
New York: Russell Sage Foundation.; 2001.
(66) Galama TJ. A contribution to health-capital theory. Rand Working Paper 2011:1-47.
(67) Galama TJ, Van Kippersluis H. Health inequalities through the lens of health-capital theory:
issues, solutions, and future directions. Research on economic inequality 2013;21:263-284.
(68) Marmot M. The influence of income on health: views of an epidemiologist. . Health affairs
2002;21(2):31-46.
(69) Toossi M. Labor force projections to 2014: Retiring boomers. Labor Force 2005(128):25-
44.
(70) West L, Cole S, GoodkinD, He W. 65+ in the United States: 2010. U S Census Bureau, U S
Government Printing Office 2014:23-212.
(71) Bosworth B BK. Changing Sources of Income among the Aged Population. Center for
Retirement Research at Boston College 2012;CRR WP 2012-27:1-34.
(72) Claxton G, Rae M, Long M,Panchal N, Damico A. (Kaiser Family Foundation). Employer
Health Benefits, 2015. Kaiser Family Foundation and Health Research and Educational Trust
2015:1-233.
(73) National Center for Health Statistics. Health, United States, 2015: With Special Feature on
Racial and Ethnic Health Disparities. U S Department of Health and Human Services 2015.
(74) Shapiro TM, Meschede T, Sullivan L. The racial wealth gap increases fourfold. Waltham,
MA: Institute on Assets and Social Policy, Brandeis University 2010.
(75) Williams DR JP. Social sources of racial disparities in health. . Health Affairs
2005;24(2):325-334.
(76) Shea DG, Miles T, Hayward M. The health-wealth connection: Racial differences. The
Gerontologist 1996;36(3):342-349.
(77) Pollack CE, Cubbin C, Sania A, Hayward M, Vallone D, Flaherty B, Braveman PA. Do
wealth disparities contribute to health disparities within racial/ethnic groups? Journal of
epidemiology and community health 2013;67(5):439-445.

19
(78) Orsi JM, Margellos-Anast H, Whitman S. Black-White health disparities in the United
States and Chicago: a 15-year progress analysis. . American Journal of Public Health
2010;100(2):349-356.
(79) Musu-Gillette L, Robinson J, McFarland J, KewalRamani, A, Zhang A, Wilkinson-Flicker
S. Status and Trends in the Education of Racial and Ethnic Groups 2016 (NCES 2016-007). U S
Department of Education, National Center for Education Statistics Washington, DC 2016.
(80) Grossman M. On the concept of health capital and the demand for health. . Journal of
Political economy 1972;80(2):223-255.
(81) Strauss J, Thomas D. Health over the life course. Handbook of development economics
2007;31(4):3375-3474.
(82) McGonagle KA, Schoeni RF. The Panel Study of Income Dynamics: Overview and
summary of scientific contributions after nearly 40 years. . Survey Research Center - Institute for
Social Research University of Michigan 2006;06-01.
(83) McGonagle KA, Schoeni RF, Sastry N, Freedman VA. The Panel Study of Income
Dynamics: overview, recent innovations, and potential for life course research. Longitudinal and
Life Course Studies 2012;3(2):268-284.
(84) Dascola M, Freedman V, Insolera N, Pfeffer F, McGonagle K, Sastry N. PSID Main
Interview User Manual: Release 2015. Institute for Social Research, University of Michigan
2015.
(85) Department of Health and Human Services. Area health and resources files (AHRF). 2015 .

20
Chapter 2
The Dynamic Relationships between Economic Indicators and Physical Health Measures
among Working-Age Adults in the United States
ABSTRACT
We examined the dynamic relationships between economic indicators and health
measures utilizing data from 8 waves of the Panel Study of Income Dynamics from 1999 to
2013. Health measures were self-rated health (SRH) and functional limitations; economic
indicators were family income, labor income and net wealth. Four approaches of panel models:1)
System-Generalized Method of Moment (system-GMM); 2) first-difference; 3) first-difference
with instrumental variables (IV); 4) Lagged fixed effects; and two standard models: 1) ordinary
least squares regression (OLS) and 2) IV OLS were used to evaluate the dynamic relationships
between economic indicators and health measures. Standard models revealed significant positive
relationships between all economic indicators and SRH and negative relationships between all
economic indicators and functional limitations. System-GMM estimators revealed a significant
positive relationships between all economic indicators and SRH. Nevertheless, only labor
income and net wealth were associated with functional limitations. SRH declined due to losses in
family income and labor income; decreases in SRH resulted in losses in family income, labor
income and net wealth. Results highlight the need for integrating the economic and health
policies and programs to prevent the adverse effects on health whenever an individual
experiences a decline in economic status or health.

21
INTRODUCTION
The relationships between economic indicators and health measures among adults living
in the United States (US) have been documented extensively in economic, epidemiological and
sociological studies (1-14). For example, in the US, Chetty and colleagues reported that men in
the top 1% of income distribution can live 15 years longer than the men in the 1% bottom of
income distribution. Similarly, women in the top 1% of income distribution can live 10 years
longer than the women in the 1% bottom of income distribution (13). While this study
highlighted the impact of economic status on mortality, there is a need for studies that evaluate
the effect of changes in economic status over time on health states other than mortality (15).
Also, further research is needed to evaluate how changes in income affect changes in health over
time and vice versa. As changes can consist of both declines and improvements in income and
health, the dynamic relationships between economic loss and health decline as well as economic
improvement and health improvement warrant examination.
The relationships between economic indicators and health may be bidirectional.
Therefore, the endogeneity between economic indicators and health need to be addressed in
estimating the effect of economic indicators on health (16,17). From an economic perspective,
healthier individuals may have access to greater economic resources because of their ability to
participate in the labor force and earn an income (16-18). On the other hand, from an
epidemiological and health policy perspectives, individuals with higher financial resources may
have better health because they have the ability to invest in their health (16-18). Some studies
have addressed this endogeneity by using statistical techniques such as instrumental variables
(IV) (3,6,12). However, it is very challenging to find valid instrument variables that have an
effect on health only through economic indicators (3,6,14).

22
Therefore, recent efforts have focused on using information available in the panel data
(example: past histories) as instrumental variables after the panel-level effects have been
removed by first-differencing (19). These models were further refined by Arellano and Bond
(20), who used the panel structure of the data and derived procedures to determine the optimal
number of lagged endogenous and exogenous variables as instruments (20,21). These estimators
have become powerful econometric tools to address the effects of endogeneity and used in many
disciplines (22,23).
Two studies (6,14) examined the causal relationships between economic indicators and
health using the Arellano-Bond dynamic panel data estimators. These two studies have reported
mixed results with one of them indicating causal effect of economic status on health (14) and the
other indicating no causal effect of economic status on health (6). Halliday reported better self-
rated health due to increases in labor income among working-age adults (21-64 years) using data
from the Panel Study of Income Dynamics. Michaud and Soest used wealth to represent the
economic status and various measures of mental and physical health as well as a composite index
to measure health based on data from the Health and Retirement Study (HRS). They concluded
that economic status did not affect health (6). The differences in findings may be due to
differences in age groups, measures of health, and economic indicators. In fact, Halliday
attributed the discrepancy in findings between his study and the study by Michaud and Soest to
differences in age group of the samples. However, it is plausible that the differences in findings
could be due to differing measurements of economic indicators and health. A major limitation of
both studies is that they did not control for other factors that may affect economic status, health
or both. Furthermore, these studies analyzed any change and did not distinguish between
economic gain and economic loss.

23
Therefore, the objective of the current study is to examine the dynamic relationships
between various measures of economic status and physical health using a sample of working-age
adults (18-64 years) in the US. The study examined the effect of positive and negative changes in
economic status on health, and improvement and decline in health on economic status.
CONCEPTUAL FRAMEWORK
This study was guided by several economic frameworks in which health capital, human
capital and financial capital interact with each other. From a health economics perspective, an
individual is born with a fixed health capital stock (health capital), which declines with age
because of biological processes (15). However, according to Grossman, health of an individual
can be improved by investing in education (human capital) because educated individuals are
more likely to improve their healthcare or effectively address/reverse a health decline. Therefore,
education rather than income or wealth is the primary driver of health (24). Case and Deaton
further suggested that the link between economic indicators and health is affected by both
education (human capital) and financial resources (financial capital). In all these models, it is
further assumed that there is an equitable distribution of health, but not human and financial
capital, at the time of birth. Individuals with lower human and financial capital may thus be more
likely to suffer earlier and more rapid declines in health, and to have poorer health at any given
point in time than those with higher human and financial capital. Galama expanded these
concepts and suggested that health may also affect economic indicators. Under his framework,
“unhealthy individuals drop out of the labor force sooner, and lose income as a result”. Case and
Deaton also acknowledged that other factors such as age may affect both health and financial
capital. In the present study, we have integrated all these frameworks and hypothesize that lower
economic status will lead to decline in health and subsequent improvement in health can lead to

24
higher economic status after adjusting for other factors that affect both economic indicators and
health.
METHODS
Study Design
The study utilized a retrospective observational longitudinal design with repeated
measures of economic indicators and health for a period of 14 years using 8 waves of the Panel
Study of Income Dynamics: 1999, 2001, 2003, 2005, 2007, 2009, 2011, and 2013. These waves
were selected due to the availability of the same sets of health variables. Data were pooled across
years and thus, each individual had 8 repeated observations.
Study Sample
The study sample consisted of heads of households (N = 2,693), who participated in all
the waves of the PSID between 1999 and 2013 and who were aged between 18-50 years in 1999.
Data Sources
The Panel Study of Income Dynamics (PSID):
The PSID was created in 1966 to help President Lyndon Johnson’s War on Poverty
(25,26). The original PSID 1968 sample was drawn from two independent samples: an over-
sample of 1,872 low-income families from the Survey of Economic Opportunity; and a
nationally representative sample of 2,930 families. The two samples constituted a national
probability sample of U.S. families in 1968 (25,26). Currently, the individuals in any panel come
from three sources: the original 1968 sample; the 1997 refresher sample of post-1968

25
immigrants; and births and marriages in existing families (25-27). In this study, both family and
cross-year individual files were combined to gather information on households.
The Area Health Resource File (AHRF):
Unemployment rates were derived from the AHRF provided by the Department of Health
and Human Services (28). We linked the state-specific metro-level unemployment rate to the
PSID by state and metro status by using five-digit Federal Information Processing Standard
(FIPS) codes.
Measures
Health Status Measures
Self-rated health (SRH): PSID queried each respondent about “say your health in
general is excellent, very good, good, fair, or poor?” This SRH was coded on a scale of 1 to 5 (5
for excellent, 4 for very good, 3 for good, 2 for fair, and 1 for poor). Ware and colleagues
transformed the SRH to a 0-100 scale using a linear relationship between item scores and the
underlying health concept (29). Thus, higher scores in SRH indicate better health.
Functional limitations: PSID participants are asked about the functional limitations due
to any reported chronic condition. PSID asks respondents “How much does this condition limit
your normal daily activities?” The response is a 4-point scale: “not at all”, “just a little”,
“somewhat”, and “a lot”. Since the degree of the limitations is the purpose of this physical
measure, we coded the response of each limitation as follow: 0 for “not at all”, 1 for “just a
little”, 2 for “somewhat”, and 3 for “A lot”. Then, we summed the responses for all the
functional limitations due to asthma, arthritis, cancer, chronic obstructive pulmonary disease,
diabetes, heart disease, hypertension, stroke, memory loss and psychological disorders. Finally,

26
we standardized the sum by transforming the sum of the raw scores to a 0 to 100 scale using the
following formula:
Functional Limitation score = (Actual raw score)−(Minimum score)
(Maximum score)−(Minimum Score) × 100
The functional limitations scores ranged from 0 to 100, with higher scores representing higher
functional limitations.
Change in Health: a) Increases in SRH: A binary indicator variable with the value of 1
representing improvements in SRH from one wave to the next and zero representing no change
or decreases in SRH scores from one wave to the next. b) Decreases in SRH: A binary indicator
variable with the value of 1 representing decreases in SRH from one wave to the next and zero
representing no change in SRH or increases in SRH scores from one wave to the next. c) Better
functional status: A binary indicator variable with the value of 1 representing a decline in
functional limitation scores from one wave to the next and zero representing no change or
increases in functional limitation scores from one wave to the next. d) Worsening functional
status: A binary indicator variable with the value of 1 representing an increase in functional
limitation scores from one wave to the next and zero representing no change or decreases in
functional limitation scores from one wave to the next.
Economic Indicators
Family Income: In the PSID, total family income is calculated as the sum of “head/wife”
taxable income (earnings, interest and dividends), head/wife transfer income, taxable or transfer
income of other family unit members, head/wife social security income, and other family unit
member’s social security income. The participants reported the incomes they received in the
prior year.

27
Labor income: We measured labor income of the head of the household. Labor income
included all money earned from wages and salaries, bonuses, overtime, tips, commissions,
professional practice or any job-related income including farm or business income.
Total net wealth: In PSID, total net wealth is derived as the sum of home equity, farm or
business assets, checking or savings accounts, vehicles, stocks and bonds and net debts. Some
individuals in our study sample reported negative or zero family income (n = 15(1999) –
22(2013)), labor income (n = 154(1999) - 435(2013)) or net wealth (n = 444(1999) – 458(2013)).
In the current study, we recoded negative values to zero and added a small positive amount ($1)
to zero values.
Quintiles of Economic Indicators: We categorized family income, labor income, and net
wealth into quintiles based on the distribution of these variables in each wave. When economic
indicators were used as continuous measures, all the economic indicators were transformed into a
natural logarithmic scale.
Other Exogenous Explanatory variables: Prior literature has established that self-related
health and chronic conditions are affected by health behavior and obesity (30,31). Therefore, for
each head of the household, we measured the following variables in each wave: number of
chronic conditions categories (no condition, one condition, >= 2 chronic conditions), body mass
index (BMI) (kg/m2) (underweight<18.5], normal [18.5 – 24.9], overweight [25.0 - 29.9], or
obese [≥30.0]), smoking status (smoker, not a smoker) and alcohol use (user, non-user). Other
factors that may affect the economic status of the participants were age, marital status (married,
widowed, separated or divorced, and never married), number of children under 18 years of age,
health insurance, external financial support, and financial liabilities to others. Time-invariant

28
variables were excluded from all models because they contradict the specifications of the fixed
effects models.
Instrumental Variables: Instrumental variables (IV) were used to address the
endogeneity between economic indicators and physical health measures. For family and labor
income, unemployment rates at the metro level were used. Unfortunately, information on county
of residence is not available in PSID. However, information on Beale-Ross Rural-Urban
Continuum codes were available for all PSID participants. From AHRF (28), we derived the
average unemployment rate for each of the Beale-Ross Rural-Urban Continuum group and
linked it with PSID. We used the responses (yes/no) to big settlement from an insurance
company, or an inheritance as an instrumental variable for net-wealth.
STATISTICAL ANALYSES
Ordinary Least Squares (OLS) Regression: The specifications of this model is as
follows:
hit = β0+ β1Yit + β2Xit + μit (1)
Where hit is the health of individual i at time t. Yit is the log transformed values or
quintile categories of the economic indicators. Xit is the matrix of the other explanatory variable.
In these models, we accounted for repeated observations.
IV OLS Regression: This statistical technique was applied to address the endogeneity
between economic indicators and physical health measures due to simultaneity, omitted variables
and measurement errors. We used metropolitan area unemployment rate and inheritance as
instrumental variables for income and wealth respectively. Following is the specification of the
model:

29
Yit = γ0+ γ1Zit + ϵit
hit = β0+ β1Y
it + β2Xit + μit (2)
Where Zit represents the instrumental variables.
First-difference (FD) estimator: We used the first-difference estimator to analyze
changes in health due to change in economic status and to mitigate the concerns due to individual
fixed effects. Static linear panel data models may be inconsistent due to the time-invariant
individual’s characteristics (Fixed-effects). Those fixed-effects may be correlated with the
explanatory variables which may introduce the omitted variables bias. The first-difference
estimator can solve this problem by using the one-period changes for each individual. Using the
first-difference estimator removes the fixed individual-specific effects because they do not
change with time. The proposed model for this estimator is as follows:
∆hit = β1∆Yit + β2∆Xit + ∆μit (3)
IV FD: Combining the first-difference estimator with IVs could remove the bias due to
endogeneity between economic indicators and health measures. We used this estimator to
remove the effect of the endogeneity between economic indicators and health measures due to
reverse causality. The specification of this model is:
∆Yit = γ1∆Zit + ∆εit
∆hit = β1∆Y
it + β2∆Xit + ∆μit (4)
In the above models, we allow for clustering on the individual level in the statistical
inference.
Lagged-fixed effect estimator: Based on Michael Grossman’s conceptual framework,
the current status of health is a function of one’s past health and past economic status (i.e. t-1).
To test this, we estimated the following model:
hit = β0+ β1hit−1 + β2Yit−1 + β3Xit−1 + μit (5)

30
Arellano-Bond generalized method of moments (GMM) estimator (20): It is possible
that current health state is influenced by past health and current economic status and other
exogenous variables.
hit = β0+ β1hit−1 + β2Yit + β2Xit + μit (6)
Equation 6 does not account for: 1) the endogeneity between economic indicators and
health measures; 2) individual-specific fixed effects; 3) the endogeneity between current state of
health and lagged health status; 4) heteroscedasticity and autocorrelation within individuals; and
5) the small time dimension compared to the large individual dimension (21). To solve these
problems, we can transform the previous equation to the following:
∆hit = β1∆hit−1 + β2∆hit + β3∆Xit + ∆μit (7)
In equation 7, the first-difference estimation can address limitations 1 and 2. The
Arellano and Bond system-GMM can address limitations 3, 4, and 5. Under the Arellano and
Bond approach, lags of the dependent variable are used as instruments to compute unbiased
consistent estimates of equation (7). However, weak instruments problem may occur in the
Arellano-Bond approach because lagged values of the endogenous variables may be weakly
correlated with the regressors in the first-difference model. Thus, Blundell and Bond (Blundell &
Bond 1998) proposed a system-GMM estimator. System-GMM estimator uses lagged
differences as instruments for the level model and lagged levels as instruments for the first-
difference model. Under system-GMM estimator, economic status is considered as a
predetermined variable and all the feasible lags of economic status and health measures (t-1 and
thereafter) are used as instrumental variables. However, we found that using only four lags of
health measures as IVs increased the efficiency of the models (Based on the second order
autocorrelation test and the Hansen J statistics on overidentifying restrictions). We also applied

31
finite sample correction to the robust two-step covariance matrix calculated for system-GMM
estimator to reduce over-identification caused by too many IVs (21).
The effect of economic loss on health decline and economic gain on health
improvement: Lagged-fixed effects and first-difference estimators were used to examine the
dynamic relationships between economic loss and decline in health as well as economic gain and
health improvement. Appendix 2.1 displays the specifications of these models. All analyses were
weighted using 2013 PSID-provided longitudinal weights.
RESULTS
Characteristics of the study sample: The study sample consisted of 2,693 heads of
households, who were between ages 18 and 50 in 1999. In the study sample, 18.5% were women
and 81.5% were men. The majority of the adults in the study sample were white (75.1%) and
married (59.8%). Most lived in a metropolitan area (76.2%). Fifty-two percent were between 18-
39 years old in 1999. In the study sample, 808 adults had chronic conditions and were eligible to
respond to the functional limitations due to chronic conditions questions in 1999. The number of
adults who had chronic conditions steadily increased to 1,585 in 2013. Thus, the panel was not
balanced for functional limitations. Table 2.1 displays the weighted percentages across the 8
waves.
Economic indicators and physical health measures over time: Table 2.2 displays the
means and standard errors of actual and natural logarithmic values of labor income of the heads
of households, family income, net wealth, SRH and functional limitations across the eight waves.
There were fluctuations in the average values of economic indicators across waves. On the other
hand, SRH and functional limitations steadily deteriorated over time.

32
The adjusted relationships between economic indicators and physical health
measures: Table 2.3 summarizes the parameter estimates and standard errors of the economic
indicators (family income, labor income, net wealth) on physical health measures (SRH and
functional limitations) from the adjusted OLS, IVOLS, FD, IVFD and lagged fixed effects.
Tables 2.4 and 2.5 summarize the Arellano-Bond system-GMM estimators for SRH and
functional limitations respectively.
Labor income and health measures:
Labor income and SRH: Adjusted OLS regression that accounted for repeated
observations indicated a significant positive relationship between labor income and SRH. When
labor income was measured in terms of quintiles, SRH was higher in labor income quintiles 2
through 5 as compared to the lowest labor income quintile. These relationships between labor
income and SRH persisted in IV OLS regressions. For example, in the adjusted analyses, SRH
was higher for higher levels of labor income (𝛽
= 3.945, p < 0.01). Similarly, in the lagged fixed
effects models labor income (in quintiles) showed a significant, positive relationship with SRH.
As illustrated in Table 2.4, models using the system-GMM estimator likewise indicated a strong
positive relationship between labor income and SRH (𝛽
= 0.868 p < 0.001). In contrast, in
analyses using FD with or without IV, no significant associations between labor income and
SRH were observed.
Labor income and functional limitations: The adjusted OLS indicated significant
negative relationships between labor income and functional limitations that persisted regardless
of whether labor income was assessed as a continuous variable or in quintiles. For example,
functional limitations declined progressively with rising quintile of labor income. Parameter
estimates and standard errors of labor income from the system-GMM estimator indicated a
33
significant negative relationship between labor income and functional limitations (𝛽
= -0.515, p <
0.001) (Table 2.5). Likewise, in models using either lagged fixed effects or FD without IV,
functional limitations declined significantly with increasing labor income regardless of
measurement. However, there was no significant relationship between labor income and
functional limitations in FD models with IV.
Family income and health measures
Family income and SRH: Adjusted OLS, indicated significant positive relationships
between family income, family income quintiles and SRH. These relationships between family
income and SRH persisted in IV OLS regressions. For example, in the adjusted analyses, SRH
was higher as for higher levels of family income (𝛽
= 10.70, p < 0.01). Likewise, parameter
estimates and standard errors of family income from the system-GMM estimators (Table 2.4)
indicated that there was a significant relationship between family income and SRH (𝛽
= 0.871, p
<0.05). In contrast, analyses using lagged fixed effects and FD with and without IV indicated
that there was no significant relationship between family income and SRH.
Family Income and functional limitations: The adjusted OLS indicated significant
negative relationships between family income and functional limitations that persisted regardless
of whether family income was assessed as a continuous variable or in quintiles. For example,
functional limitations declined progressively with rising quintile of family income. In models
using lagged fixed effects and FD with and without IV, there were no significant relationships
between family income and functional limitations. Likewise, parameter estimates and standard
errors of family income from the Arellano-Bond system-GMM estimators (Table 2.5) indicated
that there was no relationship between family income and functional limitations.

34
Net wealth and health measures:
Net wealth and SRH: Adjusted OLS suggested a significant positive relationship
between net wealth (continuous or in quintiles) and SRH. We also observed a significant
relationship between net wealth and SRH (𝛽
= 0.317, p < 0.001) using system-GMM estimators.
However, the relationships between net wealth and SRH were not significant in IV OLS
regressions, lagged fixed effects models, or FD models with IV.
Net wealth and functional limitations: Adjusted OLS revealed a significant negative
relationship between net wealth (continuous or in quintiles) and functional limitations. However,
IV OLS regressions revealed a significant positive relationship between net wealth and
functional limitations. Lagged fixed effects models indicated a significant negative relationship
between net wealth and functional limitation. System-GMM estimators indicated that there was a
significant negative relationship between net wealth and functional limitations (𝛽
= -0.142, p <
0.05).
Health improvement due to gain in economic status:
In the adjusted FD analyses, increases in net wealth were associated with a 1.8 percentage
point increase in the probability of SRH improvement. In the adjusted FD analyses, the
transitioning from a lower net wealth quintile to an upper quintile was associated with a 3.8
percentage point increase in the probability of SRH improvement. In the adjusted lagged fixed
effects, gains in family (𝛽
= 0.78, p < 0.05) or labor income (𝛽
= 0.89, p < 0.05) had a positive
impact on SRH; similar results were observed when labor income was measured as quintiles.
Gains in labor income were also associated with better functional status (𝛽
= -0.936, p < 0.001).

35
Decline in health due to decline in economic status:
In the adjusted FD analyses, decreases in family income, labor income and net wealth
were associated respectively with 1.76, 2.1 and 2.2 percentage point increase in the probability of
SRH decline. The transition from an upper labor income quintile to a lower quintile was
associate with a 2.1 percentage point increase in the probability of SRH decline. Additionally,
the transition from an upper net wealth quintile to a lower quintile was associated with a 4.2
percentage point increase in the probability of SRH decline. In the adjusted FD analyses,
decreases in family income were associated with a 4.2 percentage point increase in the
probability of higher functional limitations. Furthermore, decreases in labor income or the
transition from an upper labor income quintile to a lower quintile were associated with 3.8 and
6.3 percentage points increase in the probability of higher functional limitations. In the adjusted
lagged fixed effects, the loss in family (𝛽
= -0.81, p < 0.05) or labor income (𝛽
= -0.75, p < 0.05)
was associated with declines in SRH; assessing labor and family income as quintiles yielded
similar findings. However, functional limitations worsened only with decline in labor income
(𝛽
= 0.863, p < 0.001).
The effects of health improvement and health decline on economic status:
In the adjusted FD analyses, SRH improvement was associated with significant gains in
family income and net wealth. SRH improvement increased the probability of gains in family
income and net wealth by 2.4 and 2.3 percentage points respectively. In lagged fixed effects
models, SRH improvement was associated with gains in all measures of economic status (Table
2.7). Conversely, reduction in SRH was associated with significant declines in all measures of

36
economic status in the adjusted FD analyses, but only with decreases in labor income in the
lagged fixed effect model (Table 2.7).
DISCUSSION
The current study examined the dynamic relationships between economic indicators
(family income, labor income, and net wealth) and two physical health measures (SRH and
functional limitations). Using the standard OLS models, all economic indicators showed
significant positive relationships with SRH and significant negative relationships with functional
limitations. Using the Arellano-bond system-GMM estimators, we found positive relationships
between SRH and all measures of economic status. However, we did not find a significant
relationship between family income and functional limitations. Our study results suggest that the
relationship between economic indicators and health is dependent on the health measures that
used to examine the relationship. Health is a multidimensional concept and economic indicators
seem to have different dynamic relationships with different components of health.
When changes in economic indicators were examined by economic loss and economic
gain, we found strong relationships between losses in family or labor income and health decline.
Although we do not know the reasons for economic loss, one could speculate that decline in
labor income may be due to reduced work hours or a job loss. Future studies need to examine the
reasons for decline in labor income because policy prescriptions for protection against job loss
and reduced work hours differ. It is plausible that many adults in the US experienced income
losses due to job losses because our study period overlapped with the great 2007-2009 recession
(32). Decline in labor income (or family income) due to loss of employment has important
potential implications for the future health of these adults and their families. Although
unemployment insurance may provide some relief in the short-term (33), it may not cover all the

37
hardships. For example, the majority of employed adults (58%) in the US receive employer-
sponsored health insurance (34) and may lose health insurance coverage due to loss of
employment. Such loss of insurance coverage may contribute to further deterioration in health
status due to the lack of access to medical care.
We also found that improvement in SRH led to increases in family income, labor income
and net wealth after adjusting for other factors; conversely, decreases in SRH led to declines in
family income, labor income, and net wealth. In the US, adults with chronic health conditions are
more likely to report that their health is fair or poor (35), suggesting that policies and
interventions that decrease the burden of chronic disease among working-age adults could have
significant positive effects on economic status in this population. In addition, given that SRH is
widely considered to be an excellent measure of healthcare quality in the US (36), improving the
healthcare quality in the US may likewise promote/lead to improvement in economic well-being.
The current study has several strengths. First, we examined the potential reciprocal
relationships between economic status and health using a variety of economic and health
measures. Second, this study assessed the relationship of health to both continuous and
categorical measures of economic status. Third, we controlled for a comprehensive list of other
exogenous explanatory variables, including age, number of chronic conditions, body mass index,
alcohol use, smoking status, light physical activity, marital status, number of children under 18
years of age, health insurance status, external financial support, and financial liabilities to others.
Also, by tracking individuals over a 14-year period, we were able to analyze causal relationships
between economic status and health, including bidirectional relationships. We also used dynamic
panel data estimators, specifically Arellano-Bond estimators, to overcome the limitations of lack
of readily available valid instrumental variables.

38
This study also suffers from some limitations. First, information on all variables was
based on self-reported data, raising the possibility of recall bias. Second, self-rated health status
and functional limitations may not capture the whole aspects of health. Third, although we
employed statistical techniques to remove the effects of endogeneity due to reverse causality and
omitted variables, we cannot completely eliminate these biases. Fourth, although we controlled
for fixed effects due to time-invariant factors such as sex, race/ethnicity and other contextual
factors, we did not provide the estimates of the effects of these factors. Also, the generalizability
is limited because we restricted our sample to those who were followed in all 8 waves of the
study.
CONCLUSION
Findings of this cohort study suggest a strong, bidirectional relationship between
economic status and health. Our findings suggest the need for integrating the economic and
health policies and programs to prevent the adverse effects on health whenever an individual
experiences either a decline in economic status or decline in health.

