


1
Chapter 1: Introduction
There is a shortage in practicing primary care providers in the United States
(Young, Chaudhry, Thomas, & Dugan, 2013). The Agency for Healthcare Research and
Quality (2015) estimated that there were 208,208 practicing primary care physicians in the
United States in 2010. These physicians serve a population estimated at over 317 million,
causing health care stakeholders to continue face challenges in expanding access and
availability to many health care providers (U.S. Department for Health & Human
Services, 2013a). Expanding access to health care services is not only a challenge for
national health care policymakers, but also for stakeholders in rural, urban, and suburban
communities (Grossman, 2009). U.S. health care consumers currently experience and are
predicted to continue to experience difficulties in accessing primary health care services
(Grossman, 2009). One of the United States Department for Health and Human Services
(USDHHS) Healthy People 2020 Initiatives is to increase the number of practicing
primary care providers (PCP) as part of increasing the general supply of the health care
provider workforce (U.S. Department for Health & Human Services, 2013a).
Several studies have analyzed the relationship between disparities in access to
primary care services in the United States and health insurance coverage. Grossman
(2009) evaluated local and national efforts focused on expanding access to primary health
care services, concluding that access to and utilization of primary health care services are
not guaranteed by one’s health insurance coverage. On the other hand, Collins and
O’Brien (2011) concluded from their study that individuals are unable to access health
care services largely in part due to the lack of health insurance coverage. These findings

2
suggest that some individuals are unable to access primary care services due to the lack
of health insurance, and others who have health insurance coverage may face restrictions
in the obtaining care.
According to the US Department of Health & Human Services (2013b),
approximately 83.2% of persons in the United States had medical insurance in 2008.
While the target goal of the USDHHS’s Healthy People 2020 program is to have 100% of
the population have health insurance coverage, the actual number of insured persons in
2008 represents a fairly high level of insured individuals (Derose, Gresenz, & Ringel,
2011). Despite an estimated eight out of 10 Americans having health insurance coverage
at the time of this study, many were unable to utilize the services of licensed health care
providers (Derose, Gresenz, & Ringel, 2011). According to the authors, access to care is
a multi-faceted topic which has several major contributing factors. Health insurance
coverage is only one aspect of being able to access the services of health care providers
(HCPs); another factors identified is the adequacy or lack thereof of HCPs (Derose,
Gresenz, & Ringel, 2011).
According to Boyle (2011), addressing disparities in access to care must begin
with an evaluation of basic economic principles of demand and supply. A change in one
principle often influences the other (Brock, 2012). (Boyle (2011), Cooper (2009), and
Dewitt (2010) evaluated the economic relationship between the supply and demand for
health care services. Despite these studies’ findings supporting the value of economics in
health care and the importance to continue assessing the supply of health care services,
limited literature exists on the impact policies have on the availability of health care

3
providers. Brock (2012) concluded that majority of the current recent literature only
examined the impact of demand-related health access improvement strategies and ignored
any impact these may have on the supply or adequacy of health care providers. Brock
(2012) argued that stakeholders should use proactive and “community-specific strategies”
rather than utilizing a one-size-fits-all approach (Brock, 2012, p. 30) to improve access to
health care providers.
Several reactive measures have often been developed to address HCP shortages.
Mongan and Lee (2005) examined the geographical distributions of HCP within several
states, finding a relative shortage of primary health care providers across many areas,
especially rural communities. Health legislation improving or expanding access has been
the main measure used to address primary health care provider shortages (Brock, 2012).
Legislation such as the United States Marine Hospital Service dating back from the 1700s
was implemented to improve access to health care services for service men and women in
local communities (U.S. Marine Hospital, n.d). Since then, additional policies at both the
national and state levels have been developed and implemented with the aim of
improving not only access to health care services for patients.
These policies and laws are also designed to improve the distribution and
availability of health care providers in communities across the US. For example, the
Rural Health Clinic Services Act (1977) and the Patient Protection and Affordable Care
Act (PPACA) (2010), were designed to improve access to health services for health care
consumers (Brock, 2012; Grossman, 2009; Kaplan & Brown, 2007). The Rural Health
Clinic Services Act was specifically designed to improve access to health care services

4
for residents living in rural communities in the United States, as well as to expand the
number of health care providers primarily nurse practitioners serving in these rural
communities (Mongan & Lee, 2005). Similarly, the PPACA, which was fully
implemented in 2014, was designed to expand health insurance coverage to many
uninsured Americans and to improve the distribution of the supply of health care
providers (Williams, McClellan, & Rivlin, 2010).
Boyle (2011) proposed that future research should assess the role these health
policies have had on the prevalence of health disparities. While this is a broad topic to
explore, there is limited recent literature on the potential negative effect health policies
have on the adequacy and willingness of primary care providers to deliver health care
services. Some stakeholders have contended that the lack of a national health care system
or workforce policy contribute to disparities in the supply of services by health care
providers (Trotter, 2011). Other stakeholders have openly expressed support for state-led
initiatives as the only viable resolution to address disparities in the health care workforce
(Cooper, 2009). Although both positions have been supported with evidence (Buchan,
2010; Collins & O’Brien, 2011; Cooper, 2009; & Trotter, 2011), there still exists a gap in
literature of the impact major health policies have on limiting the availability of primary
care providers. Few studies have examined the sources of the disparities in the supply of
health care services, and increasing disparities in access. No recent research has analyzed
the role health legislation implemented to expand the demand for health care services,
may have on decreasing the supply of health care services, as well as increasing
disparities.

5
The purpose of this research study was to demonstrate that recently enacted health
policies in the United States negatively impact the satisfaction of PCPs and their
practices. To date, there has been no record of a study assessing the impact health
legislation has on primary health care providers’ willingness and ability to deliver care.
Understanding the effect these legislation have on primary care providers’ practices is
very important to local and national health care policymakers. Patton and Sawicki (1993)
stated that policy analysis is a foundation for future policy development. Dunn (2004)
further explained that the assessment or evaluation of existing policy should be integrated
into any policy analysis before any changes can be made. Therefore, this study was
designed to collect information needed to and improve policy development and
evaluation processes, provide scholarly evidence for future research, and reduce
disparities in access.
Background
The practices of health care providers in the United States are governed by state
and federal laws, regulation, and professional policies (Blumenthal, 2004). Most of these
laws, regulations, and legislation have been developed and subsequently analyzed for
their focus on the demand for health services, without examination of their effect on
provider practice (Bennett, Corluka, Doherty, & Tangcharoensathien, 2012). Boyle
(2011) and Brock (2012) explained that this is a one-sided or consumer-driven analysis
that is unable to adequately address the observed disparities in access. Equal attention
should also be placed on the supply of health care services and the willingness of health
care providers to deliver these services within the scope of their education and training

6
(Green, Savin, & Lu, 2013). Limited knowledge exists on any direct impact that major
U.S. health legislation has on the practices of health care providers (Running, Hoffman,
& Mercer, 2008).
Access to health care services includes patients being able to obtain care (demand
for services), as well as the availability of health care providers delivering health care
services (supply of services). While several efforts have been implemented to improve
the utilization of health services, recent reports have indicated that individuals are unable
to obtain preventive services and sometimes significant delays in receiving care (U.S.
Department for Health & Human Services, 2013a). Additionally, current and anticipated
shortages in the primary care provider workforce, suggest a need to examine whether the
availability or willingness of primary care providers to deliver health services of HCP are
restricted by some existing health policies (Greysen, Richards, Coupet, Desai, & Padela,
2013). Recent literature has not assessed the relationship between policies and physician
availability, and how these may be contributing to disparities.
Much of the extant literature on these aspects of U.S. health care has focused on
the relationship between access to care and health insurance coverage. As reiterated by
Brock (2012), little emphasis has been on the relationship between health care legislation
and the delivery of health services by HCP. This dissertation was designed to identify the
restrictions that U.S. primary health care providers believe are the result of major health
access policies. The dissertation’s central purpose was to analyze the relationship
between major health access policies in the United States and primary health care

7
providers’ willingness and availability to deliver health care services, and to further
evaluate how these restrictions contribute to disparities in access.
Problem Statement
Health care stakeholders have identified the inadequate distribution and
availability of primary care physicians, and other health care providers across the United
States as major challenges in access to health care providers (Cooper, 2009). Sager
(2013) stated that this is a known issue but few measures have been effective in
preserving or expanding the capacity and availability of health care providers in the
United States (p. 67). Strategic efforts such as expanded educational and residency
programs, loan forgiveness, and expanded autonomy at the state and federal levels have
been implemented to improve the long-term availability of health care providers
(Jacobson & Jazowski, 2011). Despite these efforts, shortages exist in the supply of
health care providers in the United States (Iglehart, 2009).
Multiple sources have argued for reforming health care and health care
assessment in the United States. Runy (2009) argued that the US health care delivery is
mostly impacted by the availability and willingness of health care providers to provide
health services. Improving access to health services can therefore no longer be assessed
primarily by the utilization of services by consumers or patients (Levesque, Harris, &
Russell, 2013), but must also be assessed by the availability of health care providers
(Huicho, Dieleman, Campbell, Codjia, Balabanova, Dussault, & Dolea, 2010).
According to the 1993 report published by the Institute of Medicine, improving access to
health care services and providers, and eliminating health disparities can only be

8
achieved through health care reform (Institute of Medicine, 1993); decades later, this
view is still supported and encouraged (McLaughlin, 2005). However, little current
evidence has been collected to assess the impact previous reform efforts may have on the
supply of services by primary care providers.
Expanding the number of medical programs and facilities, and providing more
attractive loan forgiveness packages increases the supply of primary care providers
(Collins & O'Brien, 2011). However, as stated by Iglehart (2011), the success of these
efforts in the United States has been significantly reduced by a fragmented US health care
delivery system and its potential to limit how health care providers practice. This creates
a problem in which health care policies developed to expand or improve the availability
and utilization of health services to health care consumers, have a significant potential to
directly or indirectly restrict the types and levels of services offered by health care
providers. Limited literature exists on how these factors do or do not contributing to the
increasing prevalence of disparities in access. This dissertation was specifically designed
to address this broader research problem by describing the restrictions primary care
providers identify are the results of health policies and analyzing how these restrictions
affect access to primary care providers and contribute to disparities.
Purpose of the Study
The purpose of this study was to analyze the relationship between major health
care access policies and physician availability in the United States, with a specific focus
on how primary care providers deliver primary health care services. Understanding how
these policies are restricting the delivery of primary health care services is an important

9
requirement for informing future health policy development and implementation
processes. For the purpose of this study, a primary care provider practice was defined as
the setting in which a licensed individual trained for and skilled in comprehensive and
continuing care is willing and able to deliver health care services to the scope of their
education and training (Currie, 2013).
This dissertation includes a brief historical reflection and evaluation of several
major acts of legislation that were developed and implemented to expand access to health
services, and the impact these have on restricting the services of primary care providers.
The Institute of Medicine (1993) defined disparities in access as the lack of timely use of
personal health services that could be used in achieving the best possible outcome. While
it is important to highlight that individuals may not be able to access health services due
to the lack of health insurance coverage or the constraints associated with having this
coverage (Blumenthal, 2006), the focus of this dissertation was on the role health care
access policies play in contributing to the shortage in the primary care workforce. The
research sought to examine the relationship between the health policies highlighted in
Chapter 2, and the availability of primary care providers. Understanding this relationship
can assist policymakers develop policies that PCPs understand and support, attract and
retain practicing PCPs, and improve methods of evaluating the impact of local and
national policies on the availability of primary care providers. This research shows that
many PCPs are dissatisfied with the impact of legislation on their practices, and
experience restrictions to their services due to these policies. Health care administrators
and policymakers in their efforts to lower health care costs, reduce PCPs turnover rate,

10
improve PCPs satisfaction can utilize the findings and recommendations of this research
to PCPs availability and improve access to their services.
The purpose of this doctoral research study was to assess the relationship between
major health access legislation in the United States ,and the availability of primary care
providers, and examine the perceptions of primary care providers’ perceptions regarding
reducing disparities in access. The results of the data identify measures that can be used
by health care stakeholders to evaluate existing health policies. This doctoral research can
also be used by health policymakers in developing local, and national health care delivery
and quality improvement programs,.
Nature of the Study
I examined the views of primary care providers in the United States on the impact
several major health policies have on how they currently deliver health services,
including how these may contribute to the prevalence in disparities in access.
Additionally, I analyzed the relationship between disparities in access and health policies.
Because it was necessary to ascertain the disparities before any relationship can be
analyzed, I selected a mixed methods study design.
The preliminary analysis used to determine these health care disparities was
completed through a review of historical local, state, and national information on access
to care in the United States. The nature of the study was a mixed-methods study with a
qualitative focus. I utilized a survey to identify the types and prevalence of restrictions or
limitations primary care providers identify within their practice, followed by
semistructured interviews conducted later by phone with a small subset of the

11
participants. This qualitative focus then examined the perceptions of primary care
providers on the role these legislation play in contributing to disparities, as well as their
recommendations on how best disparities in access can be reduced or eliminated. This
mixed-methods study was consistent with the goals of understanding the current state of
the supply of primary care providers and exploring how this is impacted by major health
care legislation.
Research Questions
The research study addressed two research questions. These are:
1. What is the relationship between major health access legislation in the United
States and the availability of primary care providers?
H0: There is no relationship between health access legislation and the availability
of primary care providers to deliver services.
H1: There is a relationship between health access legislation and the availability of
primary care providers to deliver services.
2. What are primary care providers’ perceptions regarding reducing disparities in
access?
Conceptual Framework
According to Marmor and Wendt (2012), a conceptual framework serves as a
constructed map helpful in defining the relationship between an issue and its contributing
factors. In order to understand the impact health access legislation has on the willingness
of a health care provider to deliver health services to a patient, a conceptual framework
should be developed. This framework will then explore the relationship that exists

12
between these variables (Marmor & Wendt, 2012). The authors described the conceptual
framework as an action-oriented plan (Marmor & Wendt, 2012), which could promote
change in health care delivery though policy analysis and evaluation processes.
Eliminating disparities in access is one aspect of a broader policy issue related to
improving the delivery of health care services in the US (Bennett, Corluka, Doherty, &
Tangcharoensathien, 2012). One of the missions of the Healthy People 2020 program is
to strengthen and improve various healthcare policies (U.S. Department of Health &
Human Services, 2013b). One goal related to this mission is expanding access to health
care services with more effective policies (U.S. Department of Health & Human
Services, 2013b). Various health care stakeholders offer valid arguments on how this
should be achieved. One of the benefits policy evaluation provides is the opportunity to
evaluate the evidence-based strategies that have been utilized in the development of
health access policies which can be incorporated into programs or strategies aimed at
reducing disparities in access.
Disparities in access to health care services are one of the issues health care
stakeholders are attempting to address (Currie, 2013). Patton and Sawicki (1993)
recommended that the facets related to disparities in access be identified and each be
analyzed individually. One ignored topic related to disparities in access is the restrictions
health care providers face in delivering care (U.S. Department of Health & Human
Services, 2013b). This particular aspect should be analyzed in order to determine whether
health policies such as the Patient Protection and Affordable Care Act (PPACA) and

13
those under Medicare and Medicaid, are indirectly restricting access to the services of
health care providers, which may also be contributing to other health care disparities.
The availability of health care providers is only one component of health care
access (Brock, 2012). An evaluation of existing statistics on the health care workforce
and its future projections provides an opportunity to consider the impact several policies
have on where and how providers practice. To date, limited research exists on the real
impact of policies such as those developed by the Centers of Medicare and Medicaid
Services or state agencies have on the availability and willingness of primary care
providers to deliver health services. This policy analysis and evaluation framework can
provide an evidence-based platform for future research, policy development, and
evaluation. Using this framework, this doctoral study assessed the intended goal of these
health policies in comparison to their achievements (Kraft & Furlong, 2010).
Policy analysis has several functions including analyzing the components of the
policy making process, and evaluating the substantive issues within the policy (Kraft &
Furlong, 2010). Dunn (2004) stated that policy analysis and evaluation not only provides
a potential solution for achieving a specific overarching goal, but also provides guidelines
helpful in examining specific elements of a goal. A growing body of literature supports
the use of policy analysis in addressing disparities (Collins & O'Brien, 2011).
Additionally recent literature focusing on improving the US health care delivery system
highlights the need to collect and interpret information that clarifies the causes and
effects of policy issues. Chapter 2 will provide a more thorough explanation of this
framework.

14
Definition of Terms
Access: According to the healthcare access model presented by Penchansky and
Thomas (1981), access refers to the availability, affordability, accessibility, acceptability
and accommodation between the suppliers and consumers within a health care system.
For this study, the emphasis will be on availability and accessibility of primary care
providers.
Disparity: Disparity as defined by the Institute of Medicine (1993) is “a
difference in access or treatment provided to members of different racial or ethnic groups
that is not justified by the underlying health conditions or treatment of patients” (p. 19).
Health care provider: A licensed individual supplying curative, preventive, or
rehabilitative health care services in a systematic way to individuals (Iglehart, 2009). For
this study, the health care providers being assessed were primary care providers.
Health care workforce: All licensed health care providers who deliver direct
patient care and support responsibilities, including but not limited to: physicians, nurses,
nurse practitioners, optometrists, ophthalmologists, physician assistants, pharmacists,
dentists, allied health professionals, psychologists and other behavioral and mental health
professionals (de Filippi, 2010). For this study, the health care workforce under study was
limited to actively licensed and actively practicing primary care providers.
Health policy: The plans, decisions, and actions undertaken to achieve specific
health care goals within a society (Robert Wood Johnson Foundation, 2013). The policies
assessed in this study were major ones or portions that have been enacted by either the
state and or federal government whose specific goal is to improve access to health

15
services for patients or consumers. The major polices examined were the Patient
Protection and Affordable Care Act, policies developed by the Centers for Medicare and
Medicaid Services, and health reform policies developed at the state level.
Health care supply: The number of trained health care providers working in a
health care system or active in the labor market (U.S. Department of Health & Human
Services, 2013b). The specific health care supply examined in this study was the number
of actively practicing primary care physicians.
Primary care provider: A health care practitioner who sees people that have
common medical problems (Medline Plus, 2014). Primary care providers in this study are
described as physicians
practicing
family medicine, general internal medicine, or
pediatrics whose primary role includes identifying and treating common medical
conditions, provide preventative care and teach healthy lifestyle choices, assess the
urgency of patients’ medical problems, and make referrals when necessary (Medline
Plus, 2014).
Assumptions
This study used several operating assumptions. These were:
1. It was assumed that participants would be honest in their responses.
2. It was assumed that the data collection instruments used were the best possible
tools for assessing any impact major health legislation that have on the
disparities in access due to restrictions primary care providers face in their
practice.

16
3. It was assumed that any revisions made following the study would not alter
the overall intent of the instruments used in the study.
Health policies are a necessity in health care delivery, and consist of precise
actions, plans, or decisions are implemented to achieve specific health goals (Cooper,
Hill, & Powe, 2002). However as Cooper (2009) explained, the scope of their designs
can contribute to many of the challenges or issues existing in America’s health care
system. Published peer-reviewed researches with supporting and opposing views were
reviewed on the efficiency and relevance of these health policies. However, both views
can be challenged.
In order to understand whether primary care providers may be unwilling or unable
to practice due to requirements of these health care access policies, it was necessary to
examine the current state of the availability of primary care providers. Majority of the
peer-reviewed literature reflects a current and anticipated shortage of primary care
providers; however, there is little consensus on the reason for the shortage (Apodaca,
2007), and even more limited research on the post-implementation impact health policy
has on the practices of primary care providers (Shaw, 2012). Apodaca (2007) and Shaw
(2012) cautioned the development of additional legislation to address these disparities
without analysis of the failures of inefficiencies of current legislation.
Limitations
The primary limitation of this study was the small sample size that was used in
the qualitative data collection phase. The quantitative section of the study consisted of
861 primary care providers, and the qualitative section had 15 participants. As with

17
previous research that used a small sample size, the risks for bias and generalizations by
the researcher increase. While the sample intended to include primary care providers
practicing across several states, the actual geographic locations of participants can limit
or eliminate possible generalizations that can be made about the impact legislation have
on restricting the practices of PCP.
Another limitation of this study is the mix of participants who were included in
the study. Currently, primary care providers are not limited to physicians; but in some
practices these do include other health care providers such as nurse practitioners and
physician assistants. My aim as the researcher was to have a sample of only primary care
physicians. The analysis was limited to only the primary care physicians who participated
in this study.
Additionally, the different state policies in effect may limit the possible
comparisons that can be made. A purposive sampling technique was to select
participants, and while 869 respondents returned the survey, only 861 participants were
included in this study. Additional limitations of this study will be discussed further in
Chapter 3.
Scope
The scope of this study comprised of health care providers practicing in
communities in the US during the last five years. The total population identified for this
study was 1,050 primary care physicians currently listed as actively practicing on the
lists purchased from the American Medical Association and the Medical Professional
database website, www.physiciansdatabase.com. This study was limited to primary care

18
physicians. The aim of the researcher was to include primary care providers who have at
least 10 years of professional practice. Both male and female PCP practicing in sole
proprietorships, physician groups, hospital and other health care settings were included.
All participants were required to give informed consent, and no potential participants
were excluded based on race, gender, or practicing locations.
Delimitations
The study did not examine the impact of contributing factors such as malpractice
insurance on the practices of health care providers. According to the 2010 National
Healthcare Disparities Report, malpractice insurance continue to be a major obstacle for
many health care providers and do limit the type of services they provide (U.S.
Department for Health & Human Services, 2013a). As discussed in this report, this can
restrict provider practice, and in some cases prevent patients from obtaining health
services (U.S. Department for Health & Human Services, 2013a). As a result, its impact
should be assessed in disparities research. This also presents an opportunity for future
research studies.
Significance of the Study
This dissertation is unique because it addressed an underresearched area in the
United States health care delivery system (Williams, McClellan, & Rivlin, 2010). As
political, economic, social, and health discussions surrounding the implementation and
effectiveness of the PPACA continue to occur, many argue about the various potential
effects this legislation will have on health care delivery. Expanding health insurance
coverage to an additional thirty million Americans will not entirely improve the access

19
and utilization of health services by patients (Williams, McClellan, & Rivlin, 2010).
Also, increasing the number of practicing health care providers across states through loan
forgiveness, expanding the scope of practice, or the building of new health care
educations facilities, have not translated into improvements in the nation’s health care
delivery system, or disparities (Stephens & Ledlow, 2010). Despite these measures, one
of the goals of the Healthy People 2020 Initiative is expanding access to care (U.S.
Department of Health & Human Services, 2013b). The solution to reducing the
disparities in access extends beyond the expansion of health insurance coverage for
health care consumers, and expanding the supply of health care providers (Stephens &
Ledlow, 2010). Sekhri, Feacham, and Ni (2011) encouraged future research on access be
focused on understanding the factors that contribute to these disparities. One such factor
is the impact health policy has on health care providers’ ability and willingness to
practice.
The results of this study provided insights into the limitations or restrictions
health care providers identify in their practices. Findings from this study can aid health
care policymakers in examining the effectiveness of existing policies, and developing
policies that will improve access to PCP. Additionally, increased awareness on the
limitations or restrictions PCP face daily in their practices can be further assessed and
factored into strategies focused on reducing disparities in access. Programs such as the
Healthy People Initiative can include the findings of this research into future public
health goals.

20
Health care legislation will continue to be developed and implemented. However,
their influence and subsequent effect on the demand and supply for health care services
may be different than what is anticipated. If legislation continue to limit or restrict the
practices of PCP nationwide, attempts of any real health reform will be unsuccessful. For
example, if physicians continue to not see Medicaid patients due to this payer’s
reimbursement policies, or legislation continue to limit the scope of practice of nurse
practitioners; then to many health care stakeholders there will be a shortage or limited
supply of health care providers.
Social Change Implications
The PPACA was fully implemented in 2014. Many health care stakeholders agree
that more effective strategies or legislation are needed to improve access and utilization
of health services. Both proponents and opponents of this legislation agree that access to
health services will now be expanded; however, concerns exist about how this will affect
the health care workforce. With the focus on preventive care, the current shortage in the
number of primary care providers suggests that the workforce may be inadequate to meet
the current and future health needs of the population. While it is true that this and other
health policies have been implemented to expand the health care workforce, disparities in
access will remain prevalent until the restrictions PCP identify that limit the availability
of health care providers are assessed and eliminated. Any attempt to address disparities in
access should examine the supply and availability of the health care workforce through
policy analysis and evaluation.

21
According to the Walden University’s 2012-2013 catalog, positive social change
is “a deliberate process of creating and applying ideas, strategies, and actions to promote
the worth, dignity, and development of individuals, communities, organizations,
institutions, cultures, and societies. Positive social change results in the improvement of
human and social conditions” (Walden University, 2013, p. 5). This institution supports
positive social change through developing scholar practitioners. From this development,
both individuals and society can then benefit from the positive social change.
The implication for positive social change this study proposes to policy makers
and other health care stakeholders will be more effective measures and methods to
analyze and evaluate the impact of existing health care access policies. Through policy
analysis and evaluation, health care stakeholders can develop new legislation that will
reduce the disparities in access to health services and providers. Identifying the
relationship between major health legislation and the adequacy and availability of health
care providers to practice, can not only add to the scholarly literature library, but also
improve access to health services, reduce some health disparities, as well as improve the
quality of services delivered.
Summary and Transition
The purpose of this chapter was to provide the background for the study.
Additionally, this chapter sought to clarify that the study will examine the relationship
between several major health legislation and the practices of health care providers. The
chapter also presented the research question and the research design that were used to
answer these research questions. The conceptual framework and the definition of key

22
terms were also presented. Included in this chapter were also the scope, limitations,
purpose, and the delimitations of the study. The implications for social change or the
benefits that could be gained from conducting the study were also discussed. The next
chapter, Chapter 2, will provide an overview of literature on these health policies, and the
most recent assessment of the disparities in access to health care services.

23
Chapter 2: Literature Review
Introduction
Prior research studies on disparities in access have focused primarily on health
care consumers, or the demand and utilization of health services (Cooper, Hill, & Powe
2002; Dowell, 1987; Freed & Stockman, 2009; Pardes, 2009). While many health care
stakeholders agree that all disparities in the American health care system should be
addressed and eliminated (Freed & Stockman, 2009), recent data published by the United
States Department of Health and Human Services shows increasing trends in several
health disparities (U.S. Department of Health & Human Services, 2013b). The
persistence of these disparities over many years has led U.S. policymakers to develop and
implement several health policies intended to expand access and utilization of health care
services (Collins & O'Brien, 2011). While there are such policies identified, this study
focused primarily on the Patient Protection and Affordable Care Act (PPACA).
Several authors have debated the need for the United States to have a national
health care providers’ workforce policy managing the distribution of providers across the
US. Cooper and Aiken (2006) argued that disparities in health care access in the U.S.
remain prevalent due to the lack of a national policy managing the supply of health care
providers in the United States. Apodaca (2007) and Runy (2009) cautioned against the
addition of such a policy, stating that disparities continue to exist in the United States
because the influence that existing health policies have on the daily practices and the
supply of health care providers remain underassessed and misunderstood. As explained
by Grumbach (2002) and Runy (2009), little is known about the actual impact health

24
policies have on provider practice, and how these contribute to the statistics in disparities
in access. Policies increasing the number of available health care providers and the
number of insured individuals in the United States have not translated to significant
reduction in the levels of disparities in access (Runy, 2009).
The Centers for Disease Control and Prevention published its Health and
Disparities and Inequalities Report (CHDIR) in , 2011. This report highlighted the
disparities in health care access in the US, though unacceptable were correctable. One of
the findings in the CHDIR report was the increasing statistics in disparities in access to
health care services for both individuals with and without health insurance coverage
(United States Department of Health and Human Services, 2011). Despite progress made
in increasing the number of practicing health care providers, health care facilities, and the
number of insured individuals, the report states that these have not resulted in eliminating
much of the disparities in access (United States Department of Health and Human
Services, 2011).
There were two purposes for conducting this research. The first goal was to
identify some of the major national health policies that have been developed and enacted
in the United States specifically to improve access to care, and to evaluate their effect on
the practices of primary care providers. The other goal of the study was to determine the
relationship that exists between these policies and disparities in access to health care
services. The literature review shows the attempts to improve access to health care
providers, the inadequacy in evaluating the effectiveness of health legislation, a reflection

25
on historical health legislations, and a discussion on current literature on legislation and
the health care provider workforce.
The Literature Review Process
The search process to ascertain scholarly resources on health care legislation,
primary care providers’ availability and supply, and disparities in access in the United
States used several databases, works by key authors, and organizational websites. The
database and database search tools used for this search were: Academic Search Complete,
Business Source Complete, CINAHL, Cochrane Database of Systematic Reviews, Health
and Psychosocial Instruments, Health Source, Google Scholar, JAMA Online,
MEDLINE, NHS Economic Evaluation, Nursing & Allied, Ovid Nursing articles, Policy
File, ProQuest, PubMed, Sage, and Science Direct, were used. Literature from the U.S.
Department of Health and Human Services, specifically including the Agency for
Healthcare Research and Quality (AHRQ), Centers for Disease Control and Prevention
(CDC), Centers for Medicare & Medicaid Services (CMS), Healthy People, and the
National Institute of Health (NIH) were also reviewed. I also used several databases
providing access to peer-reviewed journals such as Health Affairs, National Center for
Biotechnology Information (NCBI), and the New England Journal of Medicine, plus
websites of organizations such as The Commonwealth Fund, The Henry J. Kaiser Family
Foundation, and The Robert Wood Johnson Foundation, as well states’ Departments of
Health, and the Florida Council of Advanced Practice Nurses political Action Committee
websites.

26
A major goal of the literature review was to identify and synthesize recent
information and data concerning issues affecting U.S. primary care providers’
professional practices, with a specific focus on policy-related issues. Several professional
publications were review to understand health care legislation, its scope, and its impact
on health care delivery. Search terms used included, barriers and opportunities in
accessing health services, , future predictions of health care workforce, health care
access, health care delivery challenges, health care legislation, health care policy, health
care provider workforce, health care reform, improving access, Patient Protection and
Affordable Care Act, physician workforce, primary care provider, primary care supply,
shortage of primary care providers. Combined search terms included, Affordable care
act and primary care providers, governance and health care supply, health policy and
physician workforce, policy development and implementation process, policy evaluation
and policy analysis, restrictions and expanding health care provider workforce, and
reimbursement methods and provider satisfaction. Limited research on many of these
topics were available for the past five years. The date range was expanded to analyze the
history of health reform and allow a reflection on previous legislation.
Topics Reviewed
This literature review provides a reflection of some policies that were
implemented to expand access to health care services in the United States over the last
three centuries. It begins with the identification and reflection of a few major health care
policies. It also explores the basic tenets of health policy development and analysis, and
how these may have contributed or continue to contribute to the design and current state

27
of the US health care delivery system (Kraft & Furlong, 2010). The review then focuses
on these health policies and their possible relationship with disparities in health care
access.
The literature review documents research on access to health care services
(Maxwell, Cortes, Schneider, Graves, & Rosman, 2011), improvements in access in
American communities (Sekhri, Feachem, & Ni, 2011), the expansion of existing health
policies, and the development of new ones (Abood, 2007). Despite a wealth of literature
focusing on patients’ access to health care services, little has examined the impact health
care legislation has on the daily practices of primary health care providers (Brock, 2012).
The focus of this study was to evaluate the role these policies may play in contributing to
the prevalence in health care access disparities.
This chapter also focuses on literature related to the conceptual framework of
health politics and planning, policy development and evaluation, and health care access.
In addition, recent data on health care access in this country was also reviewed. The
literature review also explores the challenges and complexities in delivering health care
services in this country. As health care delivery is centered on access, quality, and cost,
advances in one area often do not result in improvements in the others. Health reform in
its purest sense should improve all areas not only for health care consumers, but also
health care suppliers and providers. Although policymakers develop health policies often
with a clear intent, this review will find that these policies sometimes produce unexpected
and often ignored consequences.

28
Policy Analysis
Policy analysis examines the issues and the development of recommendations that
will create solutions to correct the issues (Bennett, Corluka, Doherty, &
Tangcharoensathien, 2012). Policy analysis in health care provides the structure for
synthesizing the issues (Bennett et al., 2012). Considered to be a plan of action, health
care policymakers and stakeholders work together to create a product (the legislation),
which becomes the response to the problem (Bennett et al., 2012). One of the major
deficiencies in the health care delivery system in the US according to Bgeman (1950) and
Goodman & Fisher (2008) is the inability of many Americans to access the services of
health care providers. For many years, health care policymakers interpreted programs
increasing the supply of health care providers such as medical loan forgiveness and
attractive repayment plans, and the expansion of medical school programs as adequate
health care provider expansion measures (Bgeman, 1950; Goodman & Fisher, 2008). For
many decades, health care policymakers and other stakeholders forecasted improved
access primarily due to anticipated surpluses in physician supply (The Commonwealth
Fund, 2009). According to the Cooper (2004), “these much heralded surpluses never
materialized, and a growing body of data and opinion now point in the other direction, a
shortage in the number of practicing health care providers” (p. 704). A review of the
literature highlighted local and statewide policy decisions which would have supported
the view of adequate numbers of health care providers (The Commonwealth Fund, 2009).
According to Reese (2011) and Sheikh (2012), the inequitable distribution of
health care providers, uneven performance measurement and satisfaction tools for HCP,

29
the lack of motivated health care workers, as well as a severe shortage of PCP, are some
of the indicators that improving access to health care providers continues to be a major
problem for health care stakeholders. According to Sheikh (2012), a global crisis will
continue to exist as long as health care providers are unable to meet the demand for
healthcare services. The identification of these concerns is the first step in developing the
solution. Derose, Gresenz, and Ringel (2011), stated that in order to reduce disparities in
health care, it is important to first understand why there are inequities in accessing the
services of health care professionals.
Mittman and Sullivan (2011) stated that the limitations providers face in their
practices contribute to disparities in access. The ongoing discussions among
policymakers and health care stakeholders are evident, and there is a consensus that many
health care policies are considered to be only band-aids (Mittman & Sullivan, 2011).
These coverings unfortunately are no longer adequate, and legislators must consider
creating a health care delivery system that is capable of expanding access to providers’
services (Mittman & Sullivan, 2011). Improving access to care for health care consumers
and reducing disparities require a system that does not consequentially restrict suppliers
(Currie, 2013). Therefore, any future health legislation should seek to benefit both the
utilizers and suppliers of health care services.
The US health care delivery system though complex, has at its core the
relationship between health care provider and patient (Buchan, 2010). Although the US
health care delivery system has historically been physician driven, patients’ ability to
seek care and their outcomes are impacted by non-physician related factors such as

30
financial, organizational, and structural health care policies (Buchan, 2010). While the
author highlighted efforts such as increases in the number of insureds in the population or
expansion in medical training programs; there is a lack of favorable outcomes in
increasing the accessibility to health care providers (Buchan, 2010). After examining
limited research on these benefits, Buchan (2010) stated that the lack of the stability and
consistency in the practices of health care providers contribute to a broken health care
system. After reviewing the literature on the current state of the US health care system, it
is evident that any attempts at real reform should begin with an examination of health
care policies enacted within the past three centuries and their effect on the health care
provider practice.
Reflection on Historical Health Legislation
Efforts to improve health care delivery in the US have been long and have taken
various approaches. As put forward by Abood (2007), the development of health
legislation has been a contentious issue that has been sharply divided along party lines.
As elected political representatives and other health care stakeholders proposed and
developed different health legislation (Hirshfield, 1970), the approach remained
consistent, with only minor modifications (Clark, Field, Koontz, & Koontz, 1980).
According to Hirshfield (1970), health care legislation aimed at improving access to care
remained focused on the most vulnerable in our population; the indigent and the elderly.
Decades later, both the federal and state governments have developed legislation focused
primarily on the unemployed, underemployed, and elderly citizens (McIntyre, Thiede, &
Birch, 2009). However, despite the somewhat active input from health care providers in

31
the development of health care legislation (Abood, 2007), the effect of many of these
legislation on the health care workforce remains understudied and often ignored (Brock,
2012).
Major Federal Legislation
Early Health Legislation: Pre 1800s
According to Harding (1937), the first record of health legislation improving
access to health care services in the US was in 1798. This government health care plan
known as the United States Marine Hospital Service is described as the genesis of the
modern health care system in America (U.S. Marine Hospital, n.d). The first health care
legislation of this facility was the Act for the Relief of Sick and Disabled Seamen
established in 1798 which was enacted to provide health care services to service men and
women, and facilitated research, hygiene and science-based medical treatment (U.S.
Marine Hospital, n.d). As more marines were exposed to communicable illnesses, heat
and cold related sicknesses, and accidents; expanded access to health care services were
provided through the funding of wage deductions (U.S. Marine Hospital, n.d).
According to Harding (1937), this health care legislation was an important
foundation in expanding the access of health care providers, particularly primary care
physicians. Through a mobile workforce stationed where the service was in need,
physicians were ready to serve marines, and other seamen, as well as immigrants at the
ports of entry. In the early years, physicians were not appointed to a given hospital, but to
the Service as a whole. Despite its intent and benefits, this health access legislation was
constantly criticized (Harding, 1937). Some of the issues cited by the author included the

32
lack of coordination in fighting communicable diseases between health care providers
and other health care stakeholders, constant disease outbreaks, overcrowding in medical
facilities, and the expanded and overbearing work load of physicians (Bliven, Cowley,
Lovett, Soule, & Young, 1938).
Years after the implementation of this health legislation, Harding (1937) reviewed
how this legislation may have impacted access to health care services. Physicians in
particular complained about low remuneration, and their lack of participation in efforts to
further develop the system (Nyweide, Anthony, Chang, & Goodman, 2011). While
marines and other military personnel were dependent on this much needed care, this
health policy inadvertently restricted how primary care providers delivered services,
particularly by discouraging physicians through strict regulations (Bgeman, 1950).
Subsequent Amendments
Prior to this becoming the United States Public Health Service and later a part of
the United States Department of Health and Human Services (USDHHS), this health care
program was known for its bureaucratic fiscal neglect (McLaren, 2007). As additional
legislation were implemented over the years, McLaren (2007) believed that these were
done to meet political needs rather than the medical or health needs of patients and health
care providers. The author stated that despite subsequent legislation such as the
Uniformed Services Health Professions Revitalization Act of 1972; trained primary care
physicians were in short supply to meet the needs of the marine and the military.
Physicians who worked for this facility were frustrated with the legislation (Clinton,

33
1998), and military personnel and their dependents began to highlight the inadequate
access to PCP and facilities (McLaren, 2007).
Health Care in the 1900s
Fullerton (1996) examined the politics of health policies in the US over the years.
Between 1910 and 1940, Presidents Roosevelt and Coolidge proposed health legislation
that would contribute to improved access to care for many Americans (Fullerton, 1996).
These policies as presented by the author were the first attempt of national health reform,
primarily as a response to increasing health care costs, and the increasing demand for
health services by citizens (Fullerton, 1996). What was omitted from this peer-reviewed
perspective was the lack of focus on the impact these policies have on the daily practices
of health care providers. As necessary as improved access was for citizens, many of these
proposed legislation were blocked by health care providers, and with good reasons
(Bliven, Cowley, Lovett, Soule, & Young, 1938), and viewed by many other stakeholders
as primarily political allegiance buy-ins by health care consumers (Fullerton, 1996).
The literature review failed to identify any analysis or review of the impact this
legislation and its subsequent amendments have on expanding the availability of health
care providers. Failing to understand the specific reasons PCP were reluctant to deliver
services not only affects the effectiveness of this legislation, but also the development
and assessment of future legislation (Fullerton, 1996).
Initial health reform: 1950s – 1960s.
The 1950s saw the amendment of the Social Security Act which was originally
passed in 1935. The Act when initially passed focused on states providing assistance to

34
elderly individuals, unemployment assistance, aid to families with dependent children,
child and maternal welfare, public health services, as well as blind Americans (DeWitt,
2010). What was omitted was the National Health Insurance (NHI) element previously
proposed by President Roosevelt (DeWitt, 2010). When amended later, the Social
Security Act became the main payer to nursing home, and improved access to care for the
poor (DeWitt, 2010). Despite opposition by doctors (DeWitt, 2007), the Act and its
subsequent amendments impacted health care delivery and access to health services. The
primary basis for the opposition as explained by the author was stakeholders’ (primarily
physicians and physicians’ interests groups) views that this as social insurance (DeWitt,
2007).
In 1965, further amendments were made to the Social Security Act. Despite
strong opposition primarily from the American Medical Association (AMA) (Goodman
& Fisher, 2008), Medicare and Medicaid were passed by Congress and President
Johnson. According to Berkowitz (2008), this physician interest group was primarily
concerned about the role the government would play in establishing physicians’ fees;
primarily reimbursing hospitals, and the “usual and customary” fee-for-service for
doctors (p. 88). The author suggested that this health care legislation’s (especially as it
relates to Medicaid) has negatively impacted the daily practices of physician and other
health care providers, and encouraged future studies to examine the effect (Berkowitz,
2008).
A review of the literature discovered a substantial amount of information on the
payment practices of Medicare and Medicaid and their impact on access to physician

35
services, but limited resources on the daily practices of health care providers
(McLaughlin, 2005). Medicaid’s reimbursement time affects physicians’ willingness to
accept new Medicaid patients, as well as terminating care to existing Medicaid patients
(Cunningham, 2009). According to Cunningham and O’Malley (2009), increases in
reimbursement rates do not increase physicians’ participation in Medicaid. While
increasing fees has often been the primary method used by policymakers to expand the
availability of health care providers delivering health services to Medicaid enrollees
(Cunningham & O’Malley, 2009), the authors cited a study conducted by the Robert
Wood Johnson Foundation that supported the finding that the reimbursement process is a
major deterrent, as well as the administrative burden the Centers for Medicare and
Medicaid Services (CMS) place on health care providers. Despite possible corrective
methods that could be used to increase the willingness of health care providers to see
Medicaid enrollees, for example partial capitation, health insuring organizations, as well
as savings for reduced immunizations (Welch, 1990), it remains difficult to implement a
one-size fits all resolution for expanding access to primary care providers in states’
Medicaid programs.
Similar issues exist with Medicare. Continued Medicare physician payment
reform has lowered Medicare patient revenue for many physicians (Schoenman, Hayes,
& Cheng, 2001). In this research article, the authors highlighted the increasing
dissatisfaction and growing trends in physicians’ dissatisfaction for Medicare fee-for-
service health maintenance organizations (HMOs), preferred provider Organizations,
(PPOs) and other private fee-for-service providers (Schoenman, Hayes, & Cheng, 2001).

36
Webb (2010) cited an archived report published by JAMA, focusing on the inequity in
Medicare reimbursement by most primary care physicians who responded to a national
survey. Apodaca (2007) examined the inequity in Medicare reimbursements to providers.
Physicians who participated in pay-for-performance schemes are rewarded with bonus
incentive payments if the criteria are met, and those who are non-participants often face
Medicare cuts (Apodaca, 2007). The recent fiscal cliff situation at the beginning of 2013
in the US also presented the potential impact Medicare policies have on the practices of
health care providers (Zimlich, 2012). According to the author, Medicare reimbursement
rates could have been reduced by an estimated 27%, which could impact not only affect
Medicare patients’ access to hospitals but also primary care physicians (Zimlich, 2012).
While this was avoided, this current legislation’s payments structure to primary care
providers, and the political climate continue to impact the types of services provided by
health care providers (Hasson & Hemphill, 2013).
Latest healthcare reform: 2010 and beyond.
In 2010, President Obama signed into law The Patient Protection and Affordable
Care Act (PPACA). While the Act addresses the future role of public programs such as
Medicaid and Medicare, improving the quality and efficiency of public health services,
revenue provisions; the focus of the Act for this exercise is the goal to expand access to
primary health care services for citizens (Healthcare.gov, 2011). As the entire Act is
gradually being implemented there are many uncertainties on the impact this will have on
access to health services and providers (Rosenbaum, 2011).

37
The PPACA will enable many uninsured Americans to obtain health insurance
coverage (Stephens & Ledlow, 2010). While this is a good step, Currie (2013) suggests
that is just the beginning of the work. Expanding coverage implies increasing demand for
health services. The challenge for health care legislators is to figure out how the present
health care system can best treat these additional patients (Frellick, 2011). The challenges
discussed earlier for Medicaid enrollees remain a major concern for this health care
legislation as it promises to expand state Medicaid programs (Currie, 2013).
On the other hand, Iglehart (2011) discussed the provisions in the Act such as
increased funding for the training of health care professionals and improvements in
Medicaid expansion reimbursement rates that can expand the availability and access to
primary care providers. According to the author, the use of other health care providers
such as advanced nurse practitioners and physician assistants as primary care providers
can expand the overall supply of HCP (Iglehart, 2011). Interestingly, this can also lead to
what the author referred to as a “turf-war”, as the scope of practice of HCP may limit any
potential progress proposed for expanding the delivery of primary care services (Iglehart,
2011). Its impact on health care supply is yet to be seen but both supporters and those
who oppose the Act agree that this will have an effect on health care delivery, and the
potential exist to add further strains to a fragile health care provider workforce.
State Legislation Expanding Access to Health Care Services
Calls for state policies aimed at improving access to health care services date back
to the early 1900s (Rosenthal, 1972). According to Rosenthal (1972), states have been the
laboratories of innovation, due to the demise of health reform at the federal level. Many

38
of the state initiatives have been models for universal health coverage, but majority of
these efforts have been defeated with the influence of health stakeholder groups such as
the AMA and other health care providers’ interest groups, labor groups, and
pharmaceutical groups (Bliven, Cowley, Lovett, Soule, & Young, 1938).
Neiditz and Fields (1993) examined the early initiatives undertaken by several
states. State health policymakers are closer to local health care stakeholders and often are
better able to handle the complexities of health reform within their specific states (Neiditz
& Fields, 1993). The authors discussed state attempts as grass root initiatives which are
less broad and more direct than federal initiatives (Neiditz & Fields, 1993). State
policymakers work closer with heath care consumers, providers, and other local
stakeholders in order to develop more effective local health policies (Neiditz & Fields,
1993). While the authors discussed this as a benefit, Riley (1995) suggested that these are
not always beneficial. The close relationships often promote the interests of one
stakeholder group over another, and often have resulted in failed attempts at true health
reform (Riley, 1995). This view supports the findings provided by Bliven, et al. (1938)
that groups such as the AMA have been successful at defeating state initiatives,
especially when these legislation potentially could impact the future reimbursement rates
their members will receive.
In 1939, California proposed compulsory health insurance for residents earning
below $3,000 annually (Belshé, 2011). This led to the first pre-payment plan for health
care providers’ services in the United States, known as The California Physicians’
Service (CPS). According to Belshé (2011), AMA encouraged the expansion of this plan

39
to other states, with the goal to capture support for its own plan. To date, California has
one of the highest degrees of managed care penetration in the country (Grumbach,
Coffman, Young, Vranizan, & Blick, 1998). The authors presented the notion that
physician-supported legislation aimed at expanding access at the state level are more
frequently enacted compared to national initiatives (Grumbach, Coffman, Young,
Vranizan, & Blick, 1998). While on one hand this is beneficial, the influence of one
group can significantly impact the type, format, and goal of the legislation, as well as
limit the analysis and review that can be performed on the effectiveness of the
policymaking process and the policy itself.
As California became a model state in improving access to care, an analysis of
physician availability and types of provider practice was done by Grumbach, Coffman,
Young, Vranizan, and Blick (1998). When compared to national figures, California had
an ample number of specialist physicians practicing between 1980 and 1985 (Grumbach,
Coffman, Young, Vranizan, & Blick, 1998). Like many other states in the country,
California has an imbalance between specialist HCP and primary care providers
(Grumbach, Coffman, Young, Vranizan, & Blick, 1998). The authors highlighted that
over 90% of the HCP educated in the state remain there to practice. As the most populous
state in the US, efforts are needed to increase the supply of PCP within the state
(Grumbach, Coffman, Young, Vranizan, & Blick, 1998). A published report by the AMA
indicated that California has the highest representation of active members in the
American Medical Association (American Medical Association, 2011). While recent
literature was not obtained showing a positive relationship between the availability of

40
health care providers and AMA supported health care policies; previous research
provides evidence that health legislation supported by this physician interest group often
is supported by many of its members and has resulted in fewer restrictions on the scope
and extent of health services offered by health care providers (Robinson & Casalino,
1995). Another finding put forth by the authors is the AMA’s effectiveness in preventing
the implementation of any sort of universal health coverage, due to its lack of support
(Robinson & Casalino, 1995). As the authors suggested, there may be a relationship
between the effectiveness of health policies and how health care providers deliver health
services (Robinson & Casalino, 1995).
In 2003, the Dirigo Health Reform Act was passed in Maine to establish universal
health coverage, via an expansion of not only public coverage, but also private-sponsored
coverage (Rosenthal & Pernice, 2004). According to a report published by The
Commonwealth Fund (2011), this legislation contained provisions that expand access to
care, improve the quality of health care offered to residents in the state, as well as contain
costs. Limited literature exists on the impact this legislation has on the practices of
Maine’s health care providers.
In 2006 several states passed health care policies improving access to care for
residents. Maryland passed the Public-Private Partnership for Health Care for All, as well
Vermont passed the Health Care Affordability Act of 2006 (Sekhri, Feachem, & Ni,
2011). Massachusetts in the same year passed health care reform legislation (Gruber,
2008), an initiative mandating new-universal health care coverage (SteelFisher, et al.,

41
2009). Since then, the state leads the nation in the lowest number of uninsured residents
in the country.
SteelFisher et al. (2009) analyzed Massachusetts physicians’ views on this health
care legislation several years after its implementation. Three categories were examined in
the study; the support of the legislation by physicians, the effect of the legislation on their
practice, and the effect on health care across the state (SteelFisher, et al., 2009).
Approximately 40% of the 2,135 respondents believe that there is a negative impact on
their practice due to the administrative burdens of the legislation (SteelFisher et al.,
2009). Less than 5% of the physicians indicated that the legislation directly restricted
access to their services (SteelFisher et al., 2009).
Policies expanding health insurance coverage for residents in these states led to an
increase in the demand for health care services, which unfortunately has not been met by
an equivalent increase in health care providers (Collins & O'Brien, 2011). According to
the authors, a survey conducted in 2008 after Massachusetts’ health care policy was
implemented, indicated a shortfall of primary care physicians and general internists
across the state (Collins & O'Brien, 2011). In a survey conducted by the Center for the
Advancement of Primary Care (CAPC), results showed a current shortage of primary
care physicians in Central Massachusetts, and physician retirements could increase the
number of primary care physician vacancies within the next five years (Collins &
O’Brien, 2011). Some of the solutions to eliminate the current and anticipated shortage in
primary care providers are increasing the reimbursement rates paid to PCPs, tuition
forgiveness programs, and expanded primary educational programs (Collins & O'Brien,

42
2011). What was missing however from this analysis was the importance of reviewing
the direct and indirect impact this legislation may have on the practices of Massachusetts’
health care providers.
Blumenthal (2004) examined the health care provider workforce and efforts
implemented to expand its size. Historically, federal policies related to the supply of
physicians are only derived after receiving evidence of the distress of the public,
professional consensus, or both (Blumenthal, 2004). States such as Florida and Texas
built medical schools and expanded education programs for nurse practitioners and
physician assistants as policymakers anticipate shortages in the supply of primary health
care providers (Blumenthal, 2004). While legislation expanding the physician supply is
welcomed, it may take many years before these new health care providers are added to
the HCP pool (Iglehart, 2009). However, according to Cunningham and O’Malley
(2009), Currie (2013), and Iglehart (2009); increased enrollment in health education and
teaching facilities, has not always translated to improved access especially in primary
care, and for Medicaid enrollees.
Legislation Initiated by Other Health Care Stakeholders
Efforts aimed at expanding health care access have also been initiated by other
non-governmental stakeholders. Many of these policies have been centered on the
development or expansion of health insurance coverage for individuals. Blumenthal
(2006) reviewed the emergence of employer sponsored health insurance in this country.
Prior to 1910, employers especially those in the mining, lumber, and railroads industries,
would develop private and voluntary programs that often prepay doctors fixed monthly

43
fees to provide medical care to employees (Blumenthal, 2006). After the depression in
the 1920s, when access to health services was restricted, the Kaiser Foundation Medical
Care Plan began arranging for voluntary salary deductions to cover workers and their
families’ health care needs; which was later expanded in 1945 (Blumenthal, 2006). Other
employers soon after began to offer health insurance coverage as in incentive for
employment.
Blumenthal (2006) primarily attributed this to two events. The first was President
Roosevelt’s decision not to pursue universal health coverage after his election victory in
1932, as well as rules enacted by the federal government beginning in the 1940s on the
treatment of health insurance deductions for tax purposes (Blumenthal, 2006). Since then,
employer-sponsored health insurance has grown and to date is the primary type of
insurance coverage for many Americans.
Organized Medicine Takes Shape
In the early 1900s, doctors began to organize within their profession (Matell,
1993). Blumenthal (2004) examined the trends in physician supply. In 1901, AMA had
approximately 8,000 physicians. Ten years later, the number was over 70,000, which
amounted to half the physicians in the country (Blumenthal, 2006). Several writers
identify this as the period of organized medicine. In 1934, the AMA adopted principles to
protect physicians’ right to set rates based on patients’ income, and to supervise voluntary
insurance; as well as declaring it unprofessional for doctors to seek profits in practicing
medicine (Matell, 1993). Yet despite this, disparities in access persisted.

44
According to Matell (1993), inadequate access to health services by patients
placed HCP under fire. The AMA’s membership by then grew significantly, and the
organization became the principal voice for the medical community (Matell, 1993). By
becoming an advocate of change, the AMA was committed to the expansion of access to
care, controlling health care costs, improving the quality of care, as well as preserving the
freedom of choice to select the types of insurance coverage and health services (Matell,
1993). By working with local health care policymakers as well as Congress, initiatives
were proposed that led to the development of new or updated health legislation.
As the AMA membership grew to over 300,000 in the early 1990s, this
organization lobbied for the creation and expansion of alternative health plans (Hansen-
Turton, Ritter, Rothman, & Valdez, 2006). As the number of employer-sponsored and
other managed care health plans increased, doctors were unable to voice any possible
grievances with the restrictions placed on them by these plans’ insurers (Schwartz, 1994).
According to the author, the then president of the AMA believed that these restrictions
were impacting the supply of health care services to patients. This led to the group’s
support of anti-trust bills that would limit the restrictions of health insurers, and allow the
implementation of less restrictive health insurance coverage for patients (Schwartz,
1994). One of these health plans was Health Access America (Burris, 1993), which was
often referred to as the AMA’s plan for health reform.
Another effort of the AMA in influencing expanding access was the development
of health policies that provided malpractice immunity to doctors working in free clinics,
as well as guidelines expanding the donations of medications (Reese, 2011). Similarly, as

45
physicians became displeased with many of the organization’s efforts, other health care
providers’ membership groups became influential in health policy development and
advocacy (Romano, 2006). What the literature review has shown is that these physicians’
membership groups are often influential in the development and passage of health policy.
Health policymakers have actively sought the support of these groups in developing
health legislation (Reese, 2011). While credible research does not exist on the effect of
these physician-sponsored and supported health legislation on the supply of health care
providers, Reese (2011) indicated that policymakers recognized that the support of these
groups is critical to the development, implementation, and effectiveness of the policy.
Romano (2006) additionally stated that when physicians’ views are represented in the
policymaking process, there is often an improvement in the supply and delivery of health
care services across communities in the US.
Current Literature on Legislation and Health Care Provider Workforce
The search for literature on the availability and practices of health care providers
was done to identify disparities in access in the United States. Much of the literature
highlighted the disparities as, the shortage of primary care providers especially in rural
areas, the disproportionate portion of specialist HCP to PCP, and the different
reimbursement practices of payers. What was common in the literature however, was the
policy implications that needed to be researched.
In examining the health care staffing position, Isgur (2008) examined the data on
the numbers of practicing health care providers. According to Isgur (2008), “the health
care industry in the US is in the middle of a full-blown workforce crisis” (p. 18). The

46
crisis is exacerbated by the inability to attract and retain health care providers(Isgur,
2008). An aging population and HCP workforce, along with increasing connections
between reimbursement and quality of care, as well as the changing dynamics in health
care delivery are some of the reasons cited by the author for these shortages. While the
author proposed intermediate fixes such as establishing performance-based metrics,
several health policies underlie the disparities in supplying health care services. A
recommendation Isgur (2008) proposed is future research analyzing how legislation
affects the availability and overall supply of health care services, in order to assist leaders
in health care in improving staffing of health care facilities.
As seen in the earlier section of the literature review, both the federal and state
governments have grappled with ways of increasing the availability and distribution of
health care providers. Although individual factors such as practice patterns and locations
must be considered, system factors such as policy development and implementation
affect the distribution of HCP (Ricketts, 2005). Ricketts (2005) stated that health
legislation developed by the Centers for Medicare and Medicaid Services, directly and
indirectly impact the availability and distribution of HCP. If this argument is indeed true,
the author believed disparities in the supply of health care services are as a result of a
fragmented health care system and an ineffective legislative development and analysis
process. The author expressed belief that credible research focusing on the impact of
policies on the maldistributions is needed to address the current disparities, and also in
the development of future legislation.

47
In attempting to assess the readiness of the US health care provider workforce in
confronting the burden of chronic disease; Bodenheimer, Chen, and Bennett (2009)
reviewed the primary and public health workforce in the country. The future projections
in chronic illnesses the authors believed will only further highlight the disparities seen
not only in physician types, but also the lack of multidisciplinary teams (Bodenheimer,
Chen, & Bennett, 2009). What the authors explained is needed is not more PCP or
specialists, but instead policy reform. Some of the recommendations proposed were
national policies limiting the number of future specialists, reform in reimbursement
methods, as well as a legislated national workforce policy that can accurately estimate the
demand for health services (Bodenheimer, Chen, & Bennett, 2009). While these were not
specifically assessed in this study, the recommendations are also supported by Cooper
and Aiken (2006) in their research article.
Staiger, Auerbach, and Buerhaus (2011) evaluated some of these
recommendations in Massachusetts several years after the state’s health care reform.
Prior to 2006, growth in HCP employment in the state lagged behind the rest of the US
(Staiger, Auerbach, & Buerhaus, 2011). Subsequent to the reform, the HCP workforce in
Massachusetts remained almost the same as the three years leading up to the reform
(Staiger, Auerbach, & Buerhaus, 2011). According to the authors, despite some measure
of payment reform in the state, as well as efforts that were put in place to meet the
increased demand for health care; the size of the physician and health care provider
workforce remained at the same levels prior to the state’s health care reform (Staiger,
Auerbach, & Buerhaus, 2011). The authors stated in their conclusion that legislation such

48
as the PPACA will have to address the effectiveness of existing health access policies if
these disparities can ever be addressed. Unfortunately, many argue that the legislation
lacks this and so research is needed not only to enhance the policy development process
but also the evaluation of the direct and indirect consequences of these policies.
Pardes (2009) examined the health reform proposals presented to Congress for
legislative action. The main omission the author cited was the soon-to-be critical shortage
of doctors facing the nation (Pardes, 2009). While many were focused on reducing and
eliminating health care disparities for health care consumers, few proposals were
presented to develop legislation that will address any possible restrictions health care
providers face as a result of health care policy requirements (Pardes, 2009). Pardes
(2009) suggested that one of the main reasons for disparities in access to health care
providers was the income disparities between specialists and PCP; in that specialist HCP
are able to charge more and pay less in costs compared to PCP. While this literature
presented areas that needed to be reformed such as reimbursement procedures and rates,
raised residency caps, as well as malpractice reform; the author failed to examine how
these could actually enhance primary care providers’ willingness to provide health care
services.
Jacobson and Jazowski (2011) examined this further after the passage of the
Patient Protection and Affordable Care Act (PPACA). The PPACA while welcomed, is
expected to further strain the PCP workforce (Jacobson & Jazowski, 2011). The authors
explained that if health care providers are not fully accepting of this new legislation, then
these HCP can quickly become marginalized in the legislative process. The literature

49
while adding to research on the state of the primary care system, failed to identify what
could be the direct causes of this marginalization. Agreeing with Pardes (2009) on the
income disparities between primary care and specialist providers, Jacobson and Jazowski
(2011) suggested that any additional legislation expanding demand for primary care
services without adequate attention to supply could possible break the delivery of
preventive care services (Jacobson & Jazowski, 2011). The authors claimed that this
could be a disruptive change to the PCP system in existence, especially in rural and
underserved areas.
Freed and Stockman (2009) examined the supply within primary care specialties.
According to the authors, data on the shortages in primary care services are not entirely
correct and are misunderstood (Freed & Stockman, 2009). There are several specialties in
primary care services, and current and proposed legislation for primary care services
often fail to address each sub-specialty within primary care (Freed & Stockman, 2009).
For example, legislation aimed at expanding access to pediatric PCP, could have an
opposite effect on adult PCP. A search for credible published research analyzing the
impact of policies on primary care sub-specialties over the past 20 years did not produce
any results. It therefore identifies that there is a gap in literature on the impact legislation
has on primary care and its sub-specialties.
Wright (2009) explored the history of four rural health care programs across the
US. Previously assessed by the National Evaluation of Rural Primary Care Programs, the
author felt it was necessary to examine why only four of the original rural primary care
programs remained sustainable while others which were assessed earlier did not (Wright,

50
2009). All the facilities faced similar issues such as community integration,
organizational and structural flexibility, as well as a comparable number of available
HCP. Wright (2009) stated that the sustainability of these and other similar health care
organizations were primarily dependent on being able to accurately assess the needs of its
workforce, and the factors that can impact how HCP practice. One of these was being
able to understand legislation in its entirety and being prepared to make changes to the
organization’s operations or structure when needed (Wright, 2009). The study while
providing health care facilities with recommendations of assessment, monitoring,
evaluation, and modification if needed was completed using secondary data and
secondary sources (Wright, 2009). The issue with this the author highlighted was the use
of data that may not have been created for the purpose of organizational operations and
sustainability (Wright, 2009). While the author discussed that these organizations’
sustainability was linked to their leaders attention to the impact of legislation, there is no
clear-cut evidence that being able to assess the impact health legislation will translate to
an organization’s long-term viability and ability to improve access to health care
providers when needed.
LeClair (2011) examined some of the biggest problems in the Minnesota Health
Care System. The two main issues identified by the author were the pricing model and
the supply model of the delivery in health care services (LeClair, 2011). The author’s
emphasis was on the pricing model used by the state and its high cost, and an analysis of
how these models are related were presented. According to the author, the Medicaid
system in Minnesota is a broken model and the more procedures performed by health

51
care providers, the higher the costs are to taxpayers (LeClair, 2011). Unfortunately this
did not transfer to higher reimbursement rates for health care providers, which has
contributed to the frustration of many health care providers to not see Medicaid patients
(LeClair, 2011). According to the author, PCP encounter difficulties in the state in how
health care services are priced, and this then constricts the supply of health care services
(LeClair, 2011). While other authors have supported this view, the author further
recommended that research be done on the possible relationship between the availability
of health care providers and the pricing models used in health care (LeClair, 2011). The
author stated that the misunderstanding of this relationship has in part contributed to the
development of less than satisfactory legislation (LeClair, 2011). The difficulty LeClair
(2011) explained in forecasting and measuring health care supply is accurately
identifying and understanding the main underlying factors. The author however, never
identified these underlying factors; and while this may be the case in this state, it may be
difficult to make generalizations in other states or types of health care facilities.
For many years, the Council of Graduate Medical Education (COGME) has been
responsible for providing evidence that support the number, types and distribution of
physicians (Deal, Hooker, Harrington, Birnbaum, Hogan, Bouchery, Klein-Gitelman, &
Warr, 2007). One of the roles this group has adopted is guiding the development of
physician workforce policies (Deal, et al., 2007). As the authors explained, previous
models used in estimating the health care workforce have provided surpluses for several
decades followed by unpredictable shortages (Deal, et al., 2007). The shift in the statistics
according to the research’s findings was primarily attributed to the failure of health

52
maintenance organizations (HMO) to limit specialty HCP as well as utilizing the
assumption that increased economic growth would increase the demand for specialized
care (Deal, et al., 2007). The authors examined the difficulties encountered in projecting
the future workforce due to the inadequacies of the models used. The literature however
presented the relationship between the demand for health services and the methods used
to develop policies expanding access the health care providers (Deal, et al., 2007). While
the focus of the research was on the rheumatology workforce, its findings support the
inability to maintain equilibrium in the delivery of health services (Deal, et al., 2007).
One of the main shortcomings is the failure of the models to incorporate the ignored or
unknown effects that influences the PCP workforce. One of these ignored effects is the
analysis of existing and future legislation, and how these impact the practice methods of
PCP.
In order to address the issues in the health care workforce highlighted in the
selected literature, research has to look at the origin or source of the issue rather than
focus only on the symptoms (Sommers, Swartz, & Epstein, 2011). Many authors,
policymakers, and other health care stakeholders identify the shortage in the health care
workforce, primarily physicians, NP, PA, and other advanced health care providers.
Previous solutions have led to the implementation of reimbursement policies, expanding
medical schools and training programs, loan forgiveness, as well as redistribution of
HCP. Despite these, shortages exists in the supply of health care services, and with the
full implementation of the PPACA approaching, many suggest the need for analysis of
health legislation on the health care workforce. This can improve forecasting models used

53
in evaluating the primary health care workforce (Hoerster, et al., 2011), and be more
valuable in the evaluation of existing policies and the development of new ones
(Sommers, Swartz, & Epstein, 2011).
Framework for Policy Analysis
Introduction
Health care research focusing on the demand and supply for health care services
have used several different frameworks to conceptualize the factors that influence health
care delivery and access to care. Most of these frameworks have focused on personal
beliefs, health insurance coverage, demographics and other “individual-level” factors
(Huicho, et al., 2010). Despite the credible amount of literature that exists on accessing
health care services, non-individual-level factors have been missing from the frameworks
used in assessing the disparities in the supply of health care services. In this section, the
framework used in this study will be discussed. In order to understand the role of health
care legislation in addressing disparities, their impact on the supply of health care
services should be reviewed.
The purpose of this study was to identify and analyze the relationship between
major health access policies and the delivery of health services by primary care
physicians, and to gather their perspectives on reducing disparities in access. This study
examined these legislation with the purpose of determining whether these policies are
associated with the increased shortage in the health care provider workforce. In order to
verify this, it was necessary to examine objectively, evidence that can be used in
developing future health policy. As the study examined both historical and current policy,

54
the conceptual framework used is policy analysis and evaluation (Patton & Sawicki,
1993).
Benefits of Policy Analysis
In order to correctly identify possible problems associated with a particular health
policy, the policy analysis process requires the researcher to divide the broad policy into
elements that can be examined on an individual basis (Patton & Sawicki, 1993). The
authors believed that the use of a systematic approach in analyzing these elements
individually can resolve complex issues (Patton & Sawicki, 1993). Additionally, having
more manageable sections or elements provides the opportunity to examine how these
parts fit into or contribute to the overall problem. Patton and Sawicki (1993) suggested
that examining each element of the problem individually can create more effective
resolutions.
Policy analysis is reactive as it is done after the problem is identified (Patton &
Sawicki, 1993). This provides the study with the opportunity to identify and examine
unique aspects of the disparities in accessing health care services, with consideration
given to both the causes and solutions to the disparities. As the study involves an
examination of existing health policies, the analysis of the process should examine
whether these legislation are as effective as initially hoped. As Dunn (2004) stated,
critically examining past and present policy requires thorough analysis. In this study,
evaluating current and past policy provided a critical analysis that may be used in future
research, and appears to support changes in the development of health policy relating to
access to care.

55
Patton and Sawicki (1993) contended that policy analysis has evolved over the
years. Despite these changes, it provides a researcher with the prospect to collect and
interpret data which can be used to develop potential solutions to the problem (Patton &
Sawicki, 1993). The opportunity exists to examine alternatives to complex issues based
on the data collected.
One goal of this study was to examine the impact of health legislation on
supplying health care services in order to provide evidence-based support for future
policy. The analysis of the data collected could provide health care policymakers with
recent practical knowledge that can be used in the process of developing future policies.
Dunn (2004) explained that the use of practical knowledge can be more effective in
addressing these issues compared to the use of mere intellectual knowledge. As a
retrospective evaluation was done, the approach will also incorporate program evaluation.
Benefits of Policy Evaluation
There are several steps involved in the policy analysis process (Patton & Sawicki,
1993). These include identifying the problem, establishing a criteria for evaluating the
problem, identifying alternatives, evaluating these alternative policies, comparing these
alternatives, and evaluating the implemented policies (Patton and Sawicki, 1993, p. 52-
53). The benefit of using this process provides one with both a pre and post analysis of
the policy issue. As stated by the authors, the policy analysis process is circular, as its
final step should result in a return to the first, as it should be determined whether or not to
continue the policy or make modification (Patton & Sawicki, 1993). The final stage as
stated by Dunn (2004) provides support or lack thereof of the effectiveness of the policy.

56
Therefore, any intended result of a health policy should incorporate the effectiveness of
the policy and any previous changes that were implemented (Dunn, 2004).
Policy evaluation also assesses how well a policy is performing (Dunn, 2004).
Health policy must be evaluated to determine whether its goals are met. Before any
changes are made in health care legislation, a pre-evaluation of existing policy should be
done (Dunn, 2004). If for example the expansion of Medicaid is resulting in restrictions
in the supply of health care services, then before any changes are made to Medicaid
enrollment and reimbursement policies, a thorough evaluation should be done on the
performance of the policy. Also, if the issue with legislation is its restrictiveness, the
evaluation process should examine what contributes to these restrictions before attempts
are made to remove these restrictions.
The Policy Analysis and Evaluation Process
There is no definitive process for analyzing and evaluating health policy (Patton
& Sawicki, 1993). The authors recommended that instead of using a standardized or one-
size-fits-all approach, the process of analysis and evaluation must be based on the nature
of the problem (Patton & Sawicki, 1993). The steps identified by the authors should be
tailored to the issue being analyzed, and is shown in Figure 1.
By beginning with the verification of the issue at hand, a researcher identifies the
various perspectives of the problem held by stakeholders. Health care research in the US
is often viewed separately from the perspectives of health care providers, consumers,
policymakers, public health representatives, and other health care stakeholders
57
Figure 1. A basic policy analysis and evaluation process.
Source: Patton and Sawicki, 1993.
Each group may have a different perspective of the causes and solutions to
improving the access to health services and reducing disparities in access. Therefore,
each stakeholder’s views should be incorporated to identify what the issue is that should
1
Verify,
Define, and
Detail the
Problem
6
Monitor
The
Implemented
Policy
2
Establish
Evaluation
Criteria
5
Display and
Distinguish among
Alternative
Policies
3
Identify
Alternative
Policies
4
Evaluate
Alternative
Policies

58
be resolved. Step 2 of the policy analysis and evaluation process is establishing
evaluation criteria (Patton & Sawicki, 1993). The criteria often developed by
policymakers should be established by all stakeholders and be relevant to address the
issue (p. 58). Not only can this create the guideline to be used, but can be utilized in
evaluating other stages such as the alternatives, once the collected data is being analyzed.
Stage 3 of this process identifies the alternative policies (Patton & Sawicki, 1993).
With the input from stakeholders welcomed, there may be several alternatives revealed
(p. 54). According to the authors, researchers should be able to also identify previously
ignored issues that may be revealed during this step.
Once the possible alternatives have been identified, they should be evaluated as
shown in step 4 in the diagram. The evaluation requires one to collect and analyze
credible data in order to display and distinguish the alternatives, which is step 5 of the
process (Patton & Sawicki, 1993). If modifications are then made to policy and these
implemented, step 6 should evaluate and monitor the policy.
Application of Conceptual Framework to This Research Study
The recent Health Care and Disparities Report (2012) provided by the Agency for
Health Care Research and Quality, as well as one of the Healthy People 2020 goals
provide support that there is a shortage in the supply of primary health care providers
across many communities. While other legislation have been implemented to increase the
number of PCP primarily serving in rural communities, the anticipated effects have not
materialized.

59
The review of the development of health policies expanding the size of the health
care workforce provided inconsistencies primarily due to the lack of a national policy
(Cooper & Aiken, 2006). As recent health policies have primarily been enacted at the
state level, the variations or stem from the inadequacy of legislation to evaluate
underlying factors both prevalent at the state and national levels such as a growing
population or increasing prevalence of chronic illnesses in the population (Levesque,
Harris, & Russell, 2013). As the authors suggested, this presents an appearance that
having an inadequate and often unsatisfied health care provider workforce is acceptable
in some communities (Levesque, Harris, & Russell, 2013). Additionally, these variations
present challenges to policymakers, health care administrators, and other stakeholders
who evaluate and enforce these policies.
If these health policies are not entirely effective and many suggest improving
them, then the question arise whether these will be in the best interest of improving health
care delivery. On one hand, some HCP view these policies as adequate and changes can
create many uncertainties leading to further disequilibrium in the system. On the other
hand, many suggest that future attempts to modify or develop new legislation are the only
way to curtail rising health care costs, and improve access and quality. While both
arguments have merit, neither opponents or proponents have provided sufficient evidence
that refutes the other.
This study sought to examine the effect these health legislation may have on
restricting the supply of health services delivered by primary care physicians. The
literature provided a definition of the problem, disparities in health care supply, and the

60
lack of credible research valuable to future policy development. Also, several
stakeholders’ perspectives were provided on what these disparities are. The literature
review provided a foundation that this research as well as future research could employ in
developing, monitoring, and evaluating current and future health policy. This conceptual
framework was used to understand how health care policy impacts the supply of health
care services.
Mixed Methods Research
While access to health services has been a widely studied topic, most of the
existing literature is centered on patients’ access to care. Only a modest amount of
literature exists on health legislation, and few have considered their impact on supplying
health care services. While there are several qualitative and quantitative studies done on
the health care workforce, and few studies done on evaluating health care legislation,
there were no mixed studies done in the past decade that relate to any of these two
variables. The use of mixed methodology in research can be both pragmatic and
advantageous (Teddlie & Tashakkori, 2009). When researchers believe that the study is
best supported by diverse sources of information from both open-ended and close-ended
measures, mixed methods research can be highly effective (Creswell, 2009). In other
health care research, a two-step approach was used; such as the administration of a
survey, followed by open-ended methods of research. Teddlie and Tashakkori (2009)
discussed that this method is often used to understand the population of interest first, in
order to collect more information on the variables being studied.

61
There is increasing interest in the field of mixed methods research in health care
research, and its emergence and practice is distinct from the two dominant paradigms;
qualitative and quantitative. According to Creswell (2009), while mixed methods
research can be complex, it is a unique research design which provides the benefit of both
qualitative and quantitative data collection and analysis in one single study. Other
proponents of mixed methods research such as Johnson and Onwuegbuzie (2004) have
clearly stated that the time has come for researchers to use mixed methods research to
bridge the division that exists between qualitative and quantitative research. This research
design can produce results that are more superior to any of the two paradigms as it allows
a researcher to use the strengths of both qualitative and quantitative methods (Johnson &
Onwuegbuzie, 2004). Also, mixed methods research captures both inductive reasoning
and deductive reasoning.
Researchers use an inductive approach to scientific inquiry by beginning with
recorded observations that are then analyzed for themes or patterns (Patton, 2002). This
approach allows these patterns or themes to be discovered without pre-determined
assumptions of what the components are. From the data, interrelationships between
variables are discovered and possible theories emerge. As is often seen in qualitative
studies, the inductive approach presents a holistic approach, as the researcher is
examining the perceptions of individuals at the present time (Miles & Huberman, 1994).
This often is considered to be more realistic as the perceptions are understood to be
changeable over time.

62
Quantitative research on the other hand often uses a deductive approach. Often
beginning with a theory, researchers deduce relationships between variables (Creswell,
2009). With this approach, the theory can either be discredited or validated based on the
results of the study. Researchers, who use this approach, determine the variables and
potential relationships between them ahead of collecting the data. The theory used will
not only guide the research problem, but also the method to be used, population of
interest, as well as the type of data collected.
Both approaches when used together provide beneficial results. An inductive
approach in a qualitative study and a deductive approach in a quantitative study, in any
order highlight the power of mixed methods research compared to either a quantitative or
qualitative research. Mixed methods also provide the benefits of identifying unknown
variables directly from the population being studied.
Summary of Literature Review
With the recent advent of another health policy’s full implementation, the
importance of evaluating health policies’ impact on the supply and availability of health
care providers is important. The literature identified the present state of the health care
workforce, the current shortage of primary health care providers, along with the
anticipated future inadequate supply awaiting the expected increase in demand.
Minimal research has been done on the disparities in the supply of health care
providers due to health legislation. The current and anticipated shortages in the primary
health care workforce indicate that no effective policies exist in understanding and
reducing disparities in health care supply. While the literature identified that the overall

63
health care workforce has been slowly increasing due to expansion in medical training
and education, the lack of credible research on the possible negative impact health
legislation may have on primary care providers supplying health services can potentially
erode any positive results of these expansion efforts
Through a focus on policy development and implementation, more effective
policies can be developed which can improve access to care for both health care
consumers and suppliers. The discussion of the conceptual framework as well as research
design for the study provided the foundation which was used to answer the research
questions. Chapter 3 focuses on the methods that were employed in conducting this study
and present justifications of why the mixed-methods approach was the most appropriate
research design for this research study.

64
Chapter 3: Research Method
Introduction to Research
Research on disparities in health care access in the United States has traditionally
focused on the availability and utilization of health care services by health care
consumers. The scope of health care providers’ practice and their availability are often
ignored in studies examining the prevalence of health care access disparities
(Bodenheimer, Chen, & Bennett, 2009). The current and predicted state of the U.S. health
care workforce suggests that efforts are needed to address the disparities in access that
currently exist, as well as improving the nation’s health care delivery system (The
Commonwealth Fund, 2009). With the passage and implementation of the Patient
Protection and Affordable Care Act (2010), understanding the role legislation play in
impacting the practices of primary care providers is critical.
This chapter provides a description of the research methodology used in
investigating the role health policies play in restricting the services primary care
providers offer and how these may be contributing to disparities in access in the United
States of America. This dissertation study used a mixed-methods approach to assess the
relationship that may exist between the supply of primary health services, disparities in
access, and health care legislation. Additionally, this chapter discusses the research
design, sampling procedures, population of interest, data collection and management of
the research, participants’ protection, and the presentations of results. This chapter
provides both the researcher and the reader with an understanding of the possible

65
limitations health care providers face in the scope of their practices and the expectations
these policies will have on disparities in access.
Research Design
A mixed-methods sequential explanatory design was used for this study. This
chapter provides all the major parts of the research project, including the sample,
measures, and methods of assignment, that were used to address the two research
questions of the study. The primary goal of this study was to analyze whether these
policies which were designed to improve the utilization of health care services may in
fact be contributing to the prevalence of disparities in access, through a focus on policy
analysis and evaluation.
According to Berman (2008), mixed methods are used extensively in behavioral,
social, and health science research to solve practical research problems. Mixed-methods
research has evolved to be a separate methodology that addresses research problems in a
way neither qualitative nor quantitative research can (Bergman, 2008). As Teddlie and
Tashakkori (2009) stated, while it is easy to think as mixed methods as collecting both
qualitative and quantitative data, this methodology should be used in research that
integrates both types of data into the research and its analysis.
Quantitative research employs both empirical methods and statements (Creswell,
2009). This approach is useful for collecting and analyzing large amounts of data,
eliminating bias, and its accuracy (Creswell, 2009); its structured data collection,
however, limits the ability of a researcher to gather information not specific to the
instrument (Punch, 2005). In health care studies, quantitative studies confine the

66
likelihood of identifying the other factors or elements that directly or indirectly impacts
the topic of interest (Punch, 2005). As a result, I did not select a strict quantitative
research design because a rich detailed explanation of the reasons for these disparities
would not have been obtained from only statistical analysis of the data.
Qualitative research on the other hand uses no-empirical methods and statements
(Creswell, 2009). When a researcher utilizes qualitative methods, they are able to identify
the themes and patterns in the data (Punch, 2005); doing so also provides the opportunity
to further understand some of the data collected. A qualitative approach is often
considered the ideal method to use in research that requires an understanding of more
than the numbers or statistics (Miles & Huberman, 1994); however, it primarily offers
subjective perspectives or views that may change rather quickly, which can restrict the
replication of findings (Punch, 2005). While qualitative analysis on the other hand can
provide this explanation, its lack of statistical inferences would have potentially reduced
the study’s credibility.
Mixed-methods research provides a researcher with richer findings, that are often
more useful than the findings of either quantitative or qualitative research alone (Rocco,
Bliss, Gallagher, & Perez-Prado, 2003). A survey instrument used in a mixed-methods
study compared to one in a quantitative study often is more useful and more accurate in
behavioral or health services research (Rocco, Bliss, Gallagher, & Perez-Prado, 2003).
Many social-science researchers believe that several health topics should not be studied
exclusively with either paradigm, but combining both quantitative and qualitative method
allows researchers to utilize the strengths of both research methods (Terrell, 2012).

67
Because the goal of this research was to identify and analyze the possible restrictions
PCP face in their practices, a sequential mixed method research design was used.
This research study utilized a survey and semistructured interviews with primary
care providers actively practicing in the United States. As a result, the depth of the data
collected depended on the participation of the primary care providers PCPs. A sample
size of 15 participants will be used in the qualitative data collection, and 861 participants
will be included in the quantitative data collection.
Role of the Researcher
The primary role of the researcher is to provide clarifications and explanations of
the specific position based on established theories or previous researches (Rudestam &
Newton, 2007). The researcher was the point of contact and source of clarification for the
participating health care providers. In-depth interviews were conducted with the
participants to gather explanations and responses provided in the survey instrument.
Primary care providers responded to the survey developed in order to identify their
understanding of the impact health care legislation have on their delivery of health care
services, and the researcher’s contact information was provided to participants if
participants required further clarification. The researcher identified and solicited research
participants, distributed and collected data, analyzed the responses of the participants, as
well as identified themes or trends in the data. The survey was developed and delivered
by mail to 1,050 primary care providers across the United States. As stated by Secomb
and Smith (2011), the researcher or the interviewer must be capable of withholding
personal perceptions and opinions.

68
Research Statement
While several health policies have been developed and enacted to improve access
to health services for consumers, reducing disparities in access remains a major challenge
for many consumers, policy makers, as well as health care providers in the United States.
The impact these legislation have on the availability and willingness of primary care
providers is understudied. The impact will be analyzed and the findings made available to
participants and other stakeholders to be included in the development and evaluation of
strategies improving health care access in the US. The goal was to determine the role
these policies have in contributing to the prevalence of disparities in access to primary
care physicians and services.
Research Questions
The purpose of this study was to answer two questions in order to analyze what
impact health legislation have on the supply of services provided by primary care
providers. The data obtained provided insight on measures that could be used to evaluate
health policy as well as develop new ones. The research questions were:
1. What is the relationship between major health access legislation in the United
States and the availability of primary care providers?
H0: There is no relationship between health access legislation and the availability
of primary care providers to deliver services.
H1: There is a relationship between health access legislation and the availability of
primary care providers to deliver services. The independent variable is health
legislation and the dependent variable is the availability of health care providers.

69
2. What are primary care providers’ perceptions regarding reducing disparities
in access?
Context and Instrumentation
This study utilized two instruments to collect the data. The survey was the
quantitative data instrument, and semistructured interviews was the qualitative data
instrument. The use of both quantitative and qualitative data collection methods provides
the opportunity to obtain an in-depth understanding of the topic of interest (Pitney,
Mazerolle, & Pagnotta, 2011). Unlike other mixed methods research design such as the
concurrent mixed method in which quantitative and qualitative data are collected and
analyzed simultaneously, sequential mixed methods allows one set of data to be collected
and analyzed at a time (Creswell, 2009). The rationale for selecting the sequential
explanatory mixed method design over the initial qualitative design was to gain greater
insights from the use of multiple data collection methods. Additionally Pitney, Mazerolle,
and Pagnotta (2011) proposed that the use of multiple sources can improve the overall
validity of the research’s findings.
Health care disparities and policy development and analysis are complex topics.
Improvements in both areas require continuous planning and evaluation. Any attempts to
examine their effectiveness require strong analytical processes and evaluation research
(Warner, Harrold, Allen, & Lyons, 2010). In explaining this point, the authors
encouraged not only the use of theoretical strategies, but also real world applications
(Warner, Harrold, Allen, & Lyons, 2010). Historically, disparities in primary health care
supply have been addressed through proposals or policies such as expansion in nurse

70
practitioner autonomy, loan forgiveness, or revisions to the educational requirements
(Fortney, Luchterhand, Zakletskaia, Zgierska, & Rakel, 2013). Despite these expansion
efforts, actions to reduce disparities, shortages in the primary health care workforce still
continue to exist (Apodaca, 2007). The use of policy analysis and evaluation can provide
additional realistic applications that can be embodied into strategies designed to reduce
these disparities and improving health care delivery.
According to Creswell (2009), the sequential explanatory research design is
useful when the need to substantiate quantitative data exists. As the literature reviewed
substantiated the current and future shortage in the health care workforce in this country,
any future research examining health care workforce should provide more than
quantitative findings. Although this research method was more rigorous in its
implementation, its benefits to explore this topic further are advantageous (Creswell,
2009).
The survey instrument utilized in this research was developed by The Physicians
Foundation. The Survey of America’s Physicians (SAP) conducted in 2012 is referred to
as one of the largest and most comprehensive research instruments used to assess
physicians’ views on health care delivery (The Physicians Foundation, 2012). The
authors of this study sought to understand the views of physicians on several issues
impacting quality and access to care (The Physicians Foundation, 2012). In this study,
almost 14,000 active physicians answered 48 multidimensional questions, many with
multiple responses (The Physicians Foundation, 2012). The SAP instrument was
formatted to collect online responses, and was configured to prevent duplicate responses

71
from the same computer. Appendix H contains the e-mail correspondence requesting and
receiving permission to use, and republish, the SAP instrument in this study. While the
SAP survey had its specific topics to be addressed, more than one-half of all physicians
indicated that they intend to make changes to their practice that will likely reduce access
to care and reduce the number of hours they see patients (The Physicians Foundation,
2012).
Expert Panel Review and Modification of Survey Instrument
After consulting with several health care experts, a modified SAP instrument and
interview questions was forwarded to eight separate experts, who had signed
confidentiality forms and who had extensive experience with health legislation and policy
review. They were asked to confirm, make additions, and recommend deletions. Their
recommendations were considered in a revision of the research instruments that was used
in this study. The modified survey will also analyze the role health access legislation
have on the practices of primary care providers. A sample of 20 health care providers was
used in field testing this modified instrument.
The experts were also asked to review the survey prior to its use for content
validity using the content validity index (CVI). The CVI is defined as “the degree to
which an instrument has an appropriate sample of items for the construct being
measured” (Polit & Beck, 2004, p. 423). A target number of 15-20 questions were
anticipated in an effort to be concise and encourage completion of the survey. The
surveys were returned to a designated post office box, where it was collected by the

72
researcher, and the returned envelope destroyed via shredding to further insure
confidentiality.
Participants
Target Population
The goal of the quantitative section of this study was to have a sample size that
would be reflective of the primary care provider workforce. The researcher utilized the
online G*Power Data Analysis program to calculate the power analysis of this potential
study. After completing the multiple sample size and power calculations for t-tests,
regression analysis, and the effect size as a function of r2, the researcher examined the
mean, mode, and median obtained from these results for the best sample size. An average
sample size of 650 participants was obtained from this power analysis.
Selection for participating in this study was based on the most current list of
primary care providers provided by the online directory service Physiciandatabases.com
and the professional medical group, American Medical Association. While there was a
cost in using this database, these lists had a wide array of primary care providers across
the United States. From these lists, a custom list of primary care providers could be
created to select participants. This provides the opportunity to derive a smaller target list
of primary care providers across the United States. As a sample size of 650 participants is
required, initially 1,050 participants were recruited. The sample was selected using
purposive sampling methods from the lists accessed from the American Medical
Association and the Medical Professional database website,
www.physiciansdatabase.com. The data was collected over a three month period.

73
According to Marshall (1996), in qualitative research, the sample size need not be
representative of the population, but rather be able to establish an in-depth understanding
of the population being researched. A sample for a qualitative study should not be too
large, as it may become difficult to extract data, or too small where it may be difficult to
achieve data saturation (Onwuegbuzie & Collins, 2007). A general rule recommended by
the authors is a sample size of 10 - 12 participants in an interview. Following this rule,
and possible time constraints the researcher used a sample size of 15 health care
providers as the sample size in the qualitative aspect of the study.
Purposive sampling is one type of nonprobability sampling methods used by
researchers to gather perspectives of a particular population (Trochim & Donnelly, 2006).
The main goal of purposive sampling was to focus on particular characteristics of a
population that are of interest, which will best enable you to answer research questions
(Trochim & Donnelly, 2006). As the success of this study depended on the perspectives
of participants, the participants in the qualitative study were limited only to health care
providers who identified restrictions in their practice caused directly or indirectly by
health access policies.
A letter of introduction was sent to participants describing the proposed research.
This letter will serve as the Consent Form for Participants / Invitation to participate in the
study and will request a response to indicate their willingness to further participate in the
study. Appendix B is the Consent Form for Participants / Invitation to Participate in this
research. Participants will also be provided with the Confidentiality Form (Appendix A).

74
These forms will describe the research purpose, reason for selecting the participants, and
any possible risk associated with the research.
Demographic Data
Demographic data was collected and categorized in the analysis of both the
quantitative and qualitative data. The decision to include demographic data is an
important component of any research on health disparities (Derose, Gresenz, & Ringel,
2011). Presenting the demographic data not only provides a description of participants,
but also allows comparisons within the population. The demographic data will be
included, presented, and discussed further in Chapters 4 and 5.
Protection of Participants
Two consent forms were provided to participants. For respondents willing to
participate in the qualitative data, one consent form should be returned with the survey,
with the PCP providing his or her contact information and availability for a telephone
interview. This consent form provided an explanation of the purpose of the research, the
reasons for selection in this study, and the role of the participants in the research. The
informed consent form also explained to the participant the opportunity to withdraw from
the study at any time, without any professional repercussions or loss of services. With an
effort to maintain participant’s confidentiality and encourage honest and open
communication, numbered identifications were used to identify each participant. All
information, recordings, transcripts, and surveys will be kept in a lockable fire-proof safe.
These will be kept for no more than 5 years, and then destroyed through a document
security agency.

75
Participants will only be identified by their specialty practice. Therefore, no
county, state, or place of employment were used to identify participants. For specific
questions or issues that were not discussed thoroughly in the semistructured interviews,
Walden University representative’s contact information was provided to all participants
who needed additional information or clarification. No research was undertaken prior to
the Walden University Institutional Review Board’s approval of the proposal for the
study. Appendix B shows the Consent Form for Participants / Invitation to Participate,
which contained Walden’s IRB approval with approval number 11-24-14-0289591 that
was distributed to all participants.
Data Collection
The data collection method that was used is the sequential explanatory design, as
outlined in Figure 2. With the existence of over forty different types of mixed method
research designs, the sequential explanatory design as discussed by Creswell and Plano-
Clark (2007) is straightforward and provides researchers with the opportunity to build
from quantitative data or instruments. According to the authors, the main feature of this
research method is its ability to explain quantitative data results. Data collection began
with the modified SAP survey instrument, shown in Appendix D. Following the analysis
of this quantitative survey instrument, semistructured interviews were administered in
order to identify common themes as well as the underlying reasons for the disparities in
the supply of health care services. The survey was mailed to participants and each
package included a self-stamped return envelope. Figure 2 highlights the steps that were
used in the sequential explanatory data collection design.
76
Figure 2. Sequential explanatory design data collection.
A total of 15 semistructured phone-interviews were conducted with health care
providers across the United States to further explore this research topic. In order to
remain consistent, all phone interviews were digitally recorded to allow the researcher to
eliminate travel and time availability difficulties. The researcher’s role was limited to the
distribution of the original surveys, conducting the semistructured interviews, and the
compilation of the data.
Analysis of the quantitative and qualitative data collected using the sequential
explanatory design will occur independently (Greene, 2007). As the author discussed, this
research design has two distinct yet interactive phases, starting with the collection and
analysis of quantitative data, followed by a qualitative analysis (Greene, 2007). Bazely
(2009) described this research design as a method to not only identify differences, but
also provide an explanation of what these differences are. Referring to this as a
connection, the author presented this method as one that can be used to discover the
quantitative findings, followed an explanation of these findings (Bazeley, 2009).
Quantitative Data Collection and Instrument
One of the purposes of quantitative data collection was to make generalizations
(Creswell & Plano-Clark, 2007). According to these authors, quantitative data collection
Quantitative
Data
Collection
and
Analysis
Follow
u
p
Qualitative
Data
Collection
and
Analysis
Interpretatio
n/
Meta-
Inference

77
methods identify a sample representative of the larger population (Creswell & Plano-
Clark, 2007). In this study, a survey was used to analyze whether or not there is a
relationship between major health access legislation and the availability of primary care
providers. The survey was designed to determine any impact health legislation may have
on the practices of these health care providers.
The survey was mailed on November 25, 2014 to primary health care physicians
using the active addresses listed in the physician database. The survey questions were
concise and intended to encourage completion of the survey. A copy of the survey is
attached as Appendix D. Composite scores were compiled for the survey questions and
incorporated in the analysis along with written comments that may be obtained in
conducting the survey.
Qualitative Data Collection and Instrument
Qualitative data collection began after completing the analysis of the quantitative
data. Following the review of the quantitative data, interviews were arranged to clarify
and identify the reasons health legislation restrict the supply of health care services.
Using a semistructured interview format, interview questions were developed signed to
solicit additional information from 15 participants. The Semi-Structured Interview
Protocol shown in Appendix E was flexible, as interview questions may be reformed
slightly based on the analysis of the quantitative data. A summary of these interviews was
then done using codes that will identify the common themes identified in the responses.
This summary allowed the researcher to compare results, in order to identify more

78
effective strategies that can be employed into the development and evaluation of health
policy.
All the interviews were administered and conducted using the telephone. These
were recorded and transcribed; and summaries created shortly after. Notes taken during
the interviews were documented along with any other information such as follow up
notes or further clarification that were needed in the data analysis. All these summaries
and notes will also be included in the final analysis. Recordings and the related
transcripts will be destroyed five years after the study’s completion. The qualitative
sample size were selected from the number of health care providers who indicated their
willingness to participate in the interviews from the surveys by returning one copy of the
Consent Form for Participants / Invitation to Participate.
The semistructured interview questions were based on the research purpose and
research questions. Additionally, questions were developed using the recommendations
provided by pre-existing literature used in the literature review. The questions were
constructed using an open ended-format to encourage reflection and discussion on the
experiences of the participants. Appendix E shows the Semi-Structured Interview
Protocol used in the qualitative data collection. This semistructured format as discussed
by Warner, Harrold, Allen, and Lyons (2010) is rigorous, but its flexibility allows a
researcher to be able to capitalize on unexpected themes.
Qualitative Data Analysis
Creswell and Plano-Clark (2007) suggested that researchers utilize the most
appropriate research instrument that can measure individual attitude and performance.

79
The sequential explanatory mixed method research design is used by researchers to
identify potential differences with the intent to explain why these differences occur
(Bazeley, 2009). In this study, the focus of the quantitative data was on the perceptions of
PCP on the issues that contributed to the types and prevalence of the disparities. Phone
interviews were conducted and the data analyzed be used to identify key themes, and
explanations provided by the health care providers. Every participant was de-identified
and only numerical codes were used as identification means. The records of this study
will remain private, and original transcription records will be securely stored in a locked
safe, accessible only by the researcher. Should this study be published in part or in its
entirety, the researcher will not include information that can be used to identify any
participant.
The primary reason for selecting this research design was to gather qualitative
data that can clarify quantitative data. With this purpose in mind, analysis of the
qualitative data were built off the results of the quantitative data. After the semistructured
interviews are completed, all the interviews were converted to a text format, with the key
ideas and phrases highlighted. The sample size was small for this section of the study,
and the coding process was conducted primarily by hand. The software program
CAQDAS was used and the themes obtained compared to those coded manually.
Integration of Data
Using a sequential explanatory mixed method research design allows one to
combine both quantitative and qualitative data in order to obtain information not only of
the prevalence of disparities in the primary health care supply, but also assess the specific

80
reasons for these disparities. The sequential explanatory research design collects
quantitative data which is then analyzed to obtain an understanding of the research
problem (Teddlie & Tashakkori, 2009). The subsequent collection and analysis of
qualitative data can then be used to further explore and explain the participants’ views,
with the intent to provide a more complete analysis of the impact of health legislation on
health care delivery. The use of multiple methods to collect data provides for verification
and validity of the data collected (Denzin, 2012). According to the author, as more
comprehensive data is collected, using triangulation methods from several sources such
as a survey and semistructured interviews, inferences can then be made based on the
analysis of the data (Denzin, 2012).
The purpose of this sequential explanatory mixed-methods study was to first
assess if health legislation are contributing to the disparities in the supply of primary
health care providers. Quantitative results were conducted using a survey, and then
several individuals were randomly selected to further explore the meaning behind the
quantitative data. This research design provides the benefit of capturing the trends or
details of research problem that may not be adequately addressed by using solely a
quantitative or a qualitative research design (Miles & Huberman, 1994).
According to Creswell (2009), in mixed method studies the emphasis should be
placed on the timing of integration. While the method used will determine when the
integration will take place, in this study the data was integrated at the point of
interpretation. The collection and analysis of the data was conducted based on each
research question.

81
Research Question 1: What is the relationship between health access legislation
and the availability of primary care providers?
H0: There is no relationship between health access legislation and the availability
of primary care providers to deliver services.
H1: There is a relationship between health access legislation and the availability of
primary care providers to deliver services. The independent variable is health
legislation and the dependent variable is the availability of health care providers.
Data to answer this question will primarily come from the survey instrument
(Appendix D). The analysis was primarily obtained from the descriptive statistics
obtained in the data. The data collection method for this question is the survey. The
relationship of these two variables, the availability and willingness of health care
providers and health legislation was analyzed using parametric and nonparametric
statistical tests. This analysis will determine any statistical significance. Obtaining a p-
value < .05, will indicate sufficient evidence to reject the null hypothesis. This was then
cross-referenced with the results of the interviews to triangulate the data. Presentation of
the results will be displayed in Chapter 4 using tables, figures, and charts.
As the surveys were administered by mail, the setting was not known. After the
final wave of survey mailing, the data was manually entered into the data management
and analysis software, SPSS and then analyzed. With regards to the interviews, these
were administered by phone, and the notes and recordings were transcribed and analyzed.
According to Agretsi (2012), the characteristics of the quantitative data must be
explored and presented, such as calculating the mean and standard deviation of variables

82
or groups. Once these are identified, further analysis should be done to compare these
characteristics (Agresti, 2012). Using the steps for quantitative analysis described by
Agretsi (2012), the data was analyzed and presented in Chapter 4. Statistical tests such as
the Pearson’s correlation test and the analysis of variance (ANOVA), along with
descriptive statistics were done using Version 21 of the software program SPSS and
conclusions made about the population. Pictorial representations such as bar graphs and
tables were also provided in Chapter 4.
Research Question 2: What are primary care providers’ perceptions regarding
disparities in access?
Data to answer this question was obtained from the responses to survey questions
eight and thirteen, and the results of the qualitative instrument, the semistructured
interview (Appendix F). The analysis was primarily through identifying the major themes
and codes.
In the qualitative analysis, the first step was to transcribe the data in its entirety.
The transcriptions will then be read and reread for the purpose of coding, identifying
themes, and making sense of the data collected. This was done without the use of
software program. The analysis of the data section will include the major themes
identified in the data transcriptions. Confidentiality was maintained with the
transcriptions as well as the audio recording. Once the transcriptions were completed,
copies were provided to all participants for their review and further commentary.

83
Quality
Despite the integration of both quantitative and qualitative data, as well as the
increasing body of literature supporting the use of mixed method studies; concerns still
exist about the study’s rigor, reliability, and validity. Researcher bias, the lack of
replicability, as well as being limited in making generalizations of the study’s findings
were few of the anticipated challenges ensuring that the research is of high quality.
However, to ensure reliability, generalizability, and validity of the quantitative research;
as well the credibility, dependability, and transferability of the qualitative research,
quality efforts were implemented.
Reliability and validity of the survey were determined using intercoder reliability
(Cook & Beckman, 2006). Using both the quantitative and qualitative data results, four
categories were used to triangulate the data results. These were: PCP interest in
influencing health policy, importance of PCP involvement in policy development and
evaluation, satisfaction of the impact of health legislation on PCP practice, and
restrictions legislation has on PCP practice. Triangulated data analysis was used to
provide a more comprehensive account of a phenomena being observed or studied using
two or more research methods. Methodical triangulation as explained by Thurmond
(2001) is using more than one research method to understand the studied phenomenon
very well Additionally, the use of multiple data collection methods were used to improve
the credibility of the study.

84
Threats to Quality
The single most important threat to the quality of the study is the use of a
modified survey instrument that has not been tested extensively. Additionally, any
reduction in the anticipated sample size can also pose a threat to the quality of the study.
The evidence of quality in a qualitative study is best described in terms of credibility,
transferability, dependability, and confirmability, and how well the results of a study
approximate the truth (Trochim & Donnelly, 2008). Because I also conducted qualitative
research, I judged the quality of the results using the applicable concepts. Evidence exists
that this study’s results are confirmable and credible and, therefore, approximate the truth
with regard to the perspectives of primary care providers’ knowledge and interest,
participation, satisfaction and restrictions of health legislation on their availability.
A target number of 15-20 questions were anticipated in an effort to be concise and
encourage completion of the survey. The surveys were returned to a designated post
office box, where it was collected by the researcher, and the returned envelope destroyed
via shredding to further insure confidentiality.
To support the quantitative and qualitative steps in this mixed method approach,
drafts of the survey and interview questions were forwarded to a group of eight health
care experts with extensive experience with health legislation and policy review. The
experts were asked to confirm, make additions, and recommend deletions. The experts’
recommendations were considered in a revision of the final survey and interview
questions. Another piece of evidence indicating both credibility and confirmability of my
results is the interview participants’ review of the qualitative data analysis.

85
Member checking was also performed. The results of the data and its analysis was
provided to participants who were asked to review and make modifications to the
abbreviated report. Member checking as posited by Trochim and Donnelly (2008)
provides the opportunity to understand and assess what participants contributed, as well
as provide the opportunity to correct errors and challenge the researcher’s interpretations.
Participants reviewed the preliminary data and provide additional comments and
feedback.
Ethical Issues
While no ethical issues were anticipated, the potential for these to arise at any
point in the process exist. I ensured that the study maintains a high ethical standard.
Confidentiality and the protection of the survey instrument were important in minimizing
potential issues. In complying with the educational requirements, written approval was
requested and obtained from Walden University’s Institutional Review Board prior to
data collection. This study received approval from Walden University’s Institutional
Review Board on November 24, 2014, with approval number 11-24-14-0289591 and
expiration date November 23, 2015. All identifying features were removed from the data
collected to ensure the confidentiality of participants.
Limitations
The study limits itself by design to only practicing primary care physicians in the
United States. No other health care provider were sought to participate in the study. As
the researcher is also employed in the pharmaceutical industry, the potential for bias
exists in the interview process. To reduce this possibility, the researcher will strictly

86
adhere to the pre-designed semistructured interview format. The researcher was available
to provide clarifications for only the specific questions or comments instead of the intent
of the interview process. Additionally, as the qualitative interviews with these health care
providers were based on the results of the quantitative data, the potential existed for
alternate comprehension and further interpretation of issue.
Summary
A sequential explanatory mixed method research design can provide an insight of
the role health policy play in restricting the supply of health care services. By first
utilizing a survey, specific policies and their effect on supply can be identified and
comparisons made. This study sought to determine the role legislation plays in the
delivery of primary health care, particularly how this restricts the availability of primary
health care providers. Conducting semistructured interviews can help in determining the
extent to which health care delivery is impacted by these legislation.
The purpose of this chapter was to explain the type of research conducted, the
population and the sample, as well as to describe how participants’ rights were protected
during and after data collection. As described in the chapter, the sequential explanatory
mixed method research design was conducted to examine the relationship between health
legislation and the supply of services provided by health care providers. In Chapter 4 an
examination of the results of the data collection will be provided, and Chapter 5 will
provide a discussion of the conclusions drawn by the researcher as well as a summary of
the dissertation.

87
Chapter 4: Results
Introduction
This study was conducted to examine the role major health policies in the United
States play in restricting the availability of primary care physicians. Statistics show
increasing disparities in access to U.S. health care services by individuals with and
without health insurance coverage (Derose, Gresenz, & Ringel, 2011). This research
study was conducted using both qualitative and quantitative data. The procedure used to
collect data for this study was guided by mixed-methods sequential explanatory design.
This research study was designed to identify the relationship between health
legislation and primary care providers’ availability, and to obtain the perspectives of
primary care providers on reducing disparities. Research Question 1 (RQ1) asked what
relationship, if any, existed between major health access legislation and the availability
of primary care providers. The modified Survey of America’s Physicians (SAP)
originally developed by the Physicians Foundation was utilized for this purpose. The
researcher sought to evaluate:
H0: There is no relationship between health access legislation and the availability
of primary care providers to deliver services.
H1: There is a relationship between health access legislation and the availability of
primary care providers to deliver services.
Research Question 2 (RQ2) asked what are the perceptions of primary care
providers’ regarding reducing disparities in access? This research question was
primarily answered using survey questions eight and 13, and the interview responses.

88
This chapter describes the data collection process including survey, interviews and
participants for this mixed method study. In addition, data analysis and its relationship
to both research questions will be presented.
Setting and Sample
I invited 1,050 U.S. primary care providers to participate in this study, using lists
that I purchased from the American Medical Association and the Medical Professional
database website at http://www.physiciansdatabase.com. The response rate was
approximately 82%, with 861 completed survey responses that I used in this sample. Each
survey mailing contained a Consent Form for Participants / Invitation to Participate, and a
self-addressed stamped return envelope. The Consent Form for Participants / Invitation to
Participate (Appendix B) provided a brief background of the study, its procedures, risks
and benefits of participating in the study, and contact information for myself and a Walden
University Institutional Review Board (IRB) representative. Semistructured interviews
were later conducted with 15 randomly selected PCP who returned a Consent Form for
Participants / Invitation to Participate form with their completed survey responses.
The researcher received 869 survey responses from the 1,050 mailings. Two of
the returned surveys were not included as more than one page of the survey was
incomplete. Six additional responses were not included in the data analysis because the
responders stated they have not practiced within the past five years. The excluded data
represent 0.92% of the total number of completed survey responses. Twenty-five
participants who returned a signed consent form were randomly selected for interview.

89
Fifteen interviews were conducted and participants were labelled Participants P1, P2, P3,
P4, P5, P6, P7, P8, P9, P10, P11, P12, P13, P14, and P15.
Survey Process
This study was conducted after I first received approval from the Walden
University Institutional Review Board, with approval number 11-24-14-0289591 and
expiring on November 23, 2015. I obtained permission from the Physician Foundation to
use the modified Survey of America’s Physicians (SAP) survey as the survey instrument
(Appendix D) was mailed to potential participants. Two Consent Form for Participants /
Invitation to Participate was included in every mailing. Each potential participant was
provided with the Consent Form, along with the survey and a self-addressed stamped
envelope. After one month, a second mailing was sent out as a reminder to participants
inviting them to participate. The survey was anonymous, and any identifying information
such as addresses or name of practices included in the responses were shredded and not
included in the presentation of data results.
Interview Process
With the informed consents obtained with the survey responses, I interviewed all
15 participants within a two-week period in January 2015. The semistructured interviews
were digitally taped and lasted an average of 1 hour and 25 minutes. The longest
interview was 1 hour and 58 minutes and the shortest interview was 55 minutes. All the
interviews took place by phone. Interview questions began with discussions under each
research question. Probes were used to gain a greater understanding of each participant‘s
response. Occasionally, additional questions were asked when further clarification was

90
needed. All participants received a transcript of the interview within one week of
completing the interview, giving them an opportunity to clarify details of the interview.
Only two participants had corrections, all the other participants indicated that the contents
of the transcript were accurate.
Data Organization and Analysis
I summarized the survey findings before comparing them with the interview
findings. I used multiple ANOVA tests, Pearson’ chi-square statistical tests, Kruskal-
Wallis H test, and Spearman’s rank correlation tests in SPSS to determine the weight of
the participants’ responses to the questions. Where possible, written comments from the
survey were categorized and reported. The purpose of organization and analysis of the
interview data was to review data and identify themes. Data related to each research
question from the interviews along with demographic information were reviewed using
constant comparative analysis and weighting the themes from the interviews. I also
selected and examined interviewee comments that supported or illustrated the identified
themes.
Demographic Findings
All participants in the survey and interviews were primary care providers
currently practicing in the United States of America. From the purchased lists of
providers, only those practicing for at least five years were selected. Tables 1 through 7
display demographic characteristics of the 861 primary care providers included in the
sample. The gender of the respondents is summarized in Table 1. The majority of the
91
sample was male primary care providers at 63.5% (n = 547) while 36.5% (n = 314) were
female respondents.
Table 1
Survey Participants by Gender
Frequency
(N = 861) %
Female 314 36.5
Male 547 63.5
Total 861 100
The average age of the total sample was 49 years old (Table 2); and the most
frequently recurring age of primary care providers was between 50-54 years with
approximately 27% of respondents (n = 229).
Table 2
Survey Participants by Age
Age Frequency (N = 861) %
Less than 40 93 10.8
40-44 166 19.3
45-49 200 23.2
50-54 229 26.6
Greater than 55 173 20.1
Total 861 100
Table 3 presents the participants’ breakdown by geographical location.
Approximately 42% (n = 364) of respondents’ practices were in urban locations, 30% (n
= 261) were in suburban locations. Approximately 28% (n = 236) of respondents’
practices were in rural areas.

92
Table 3
Survey Participants by Geographical Location of Practice
Location Frequency (N = 861) %
Rural 236 27.4
Urban 364 42.3
Suburban 261 30.3
Total 861 100
Table 4
Survey Participants by Region of Practice
Location Frequency (N = 861) %
Northeast States 93 10.8
Mid-Atlantic States 95 11.0
East North Central States 93 10.8
West North Central States 98 11.4
South Atlantic States 103 12.0
East South Central States 95 11.0
West South Central States 112 13.0
Mountain States 85 9.9
Pacific States 87 10.1
Total 861 100.0
Table 4 presents the participants’ breakdown by the state regions. Nine state
regions were used to categorize the participants. As shown in Table 4, Mountain States
had the least number of participants, 85; while the West South Atlantic States had 112
respondents.

93
Table 5
Survey Participants by Employment Setting
Employment Setting Frequency (N = 861) %
Public 219 25.4
Private 213 24.7
Owner/Partner/
Associate 147 17.1
Educator 163 18.9
Other 119 13.8
Total 861 100
Table 5 presents the participants’ breakdown by employment settings. One-fourth (n =
219) of respondents worked in public settings such as hospitals and clinics. Almost 25%
(n = 213) of respondents worked in private health care facilities. A total of 119 identified
their employment setting as other. Ninety-Five of these listed that they worked for
Accountable Care Organizations (ACO).
Survey participants were asked if they were members of professional bodies.
Approximately 59% (n = 508) stated that they were members of the American Medical
Association, 38% (n = 327) stated they were members of the American Osteopathic
Association. The remaining 3% did not answer the question or stated “Other” without
providing the name of the group they are affiliated with.

94
Table 6
Survey Participants by Hours Worked per Week
Hours Worked per Week Frequency (N = 861) %
Less than 20 189 22.0
20 – 30 230 26.7
30 – 40 245 28.5
40 – 60 157 18.2
Over 60 40 4.6
Total 861 100
Table 6 shows the responses for survey question 19, on average, how many hours do you
work per week. 664 PCP indicated that they worked less than 40 hours each week. Only
40 PCP stated that they worked greater than 60 hours each week.
Table 7
Survey Participants by Percent of Time Spent on Nonclinical Duties
% Time Spent on Nonclinical Duties Frequency (N = 861) %
None 61 7.1
Less than 25 213 24.7
25 – 50 316 36.7
Over 50 271 31.5
Total 861 100
Table 7 shows the responses obtained for survey question 20 asked, on average, what
percent of your work time do you spend on nonclinical (paperwork) duties?
Approximately 37% (n = 316) of PCP stated that they spend between 25% and 50% of
their time each week on non-clinical duties. Another 32% (n = 271) spend greater than
50% of their time on non-clinical duties.
Statistical tests were selected using Agresti’s (2013) steps for data analysis. Based
on the type of variables, the number of variables, the expected fit to the parametric or
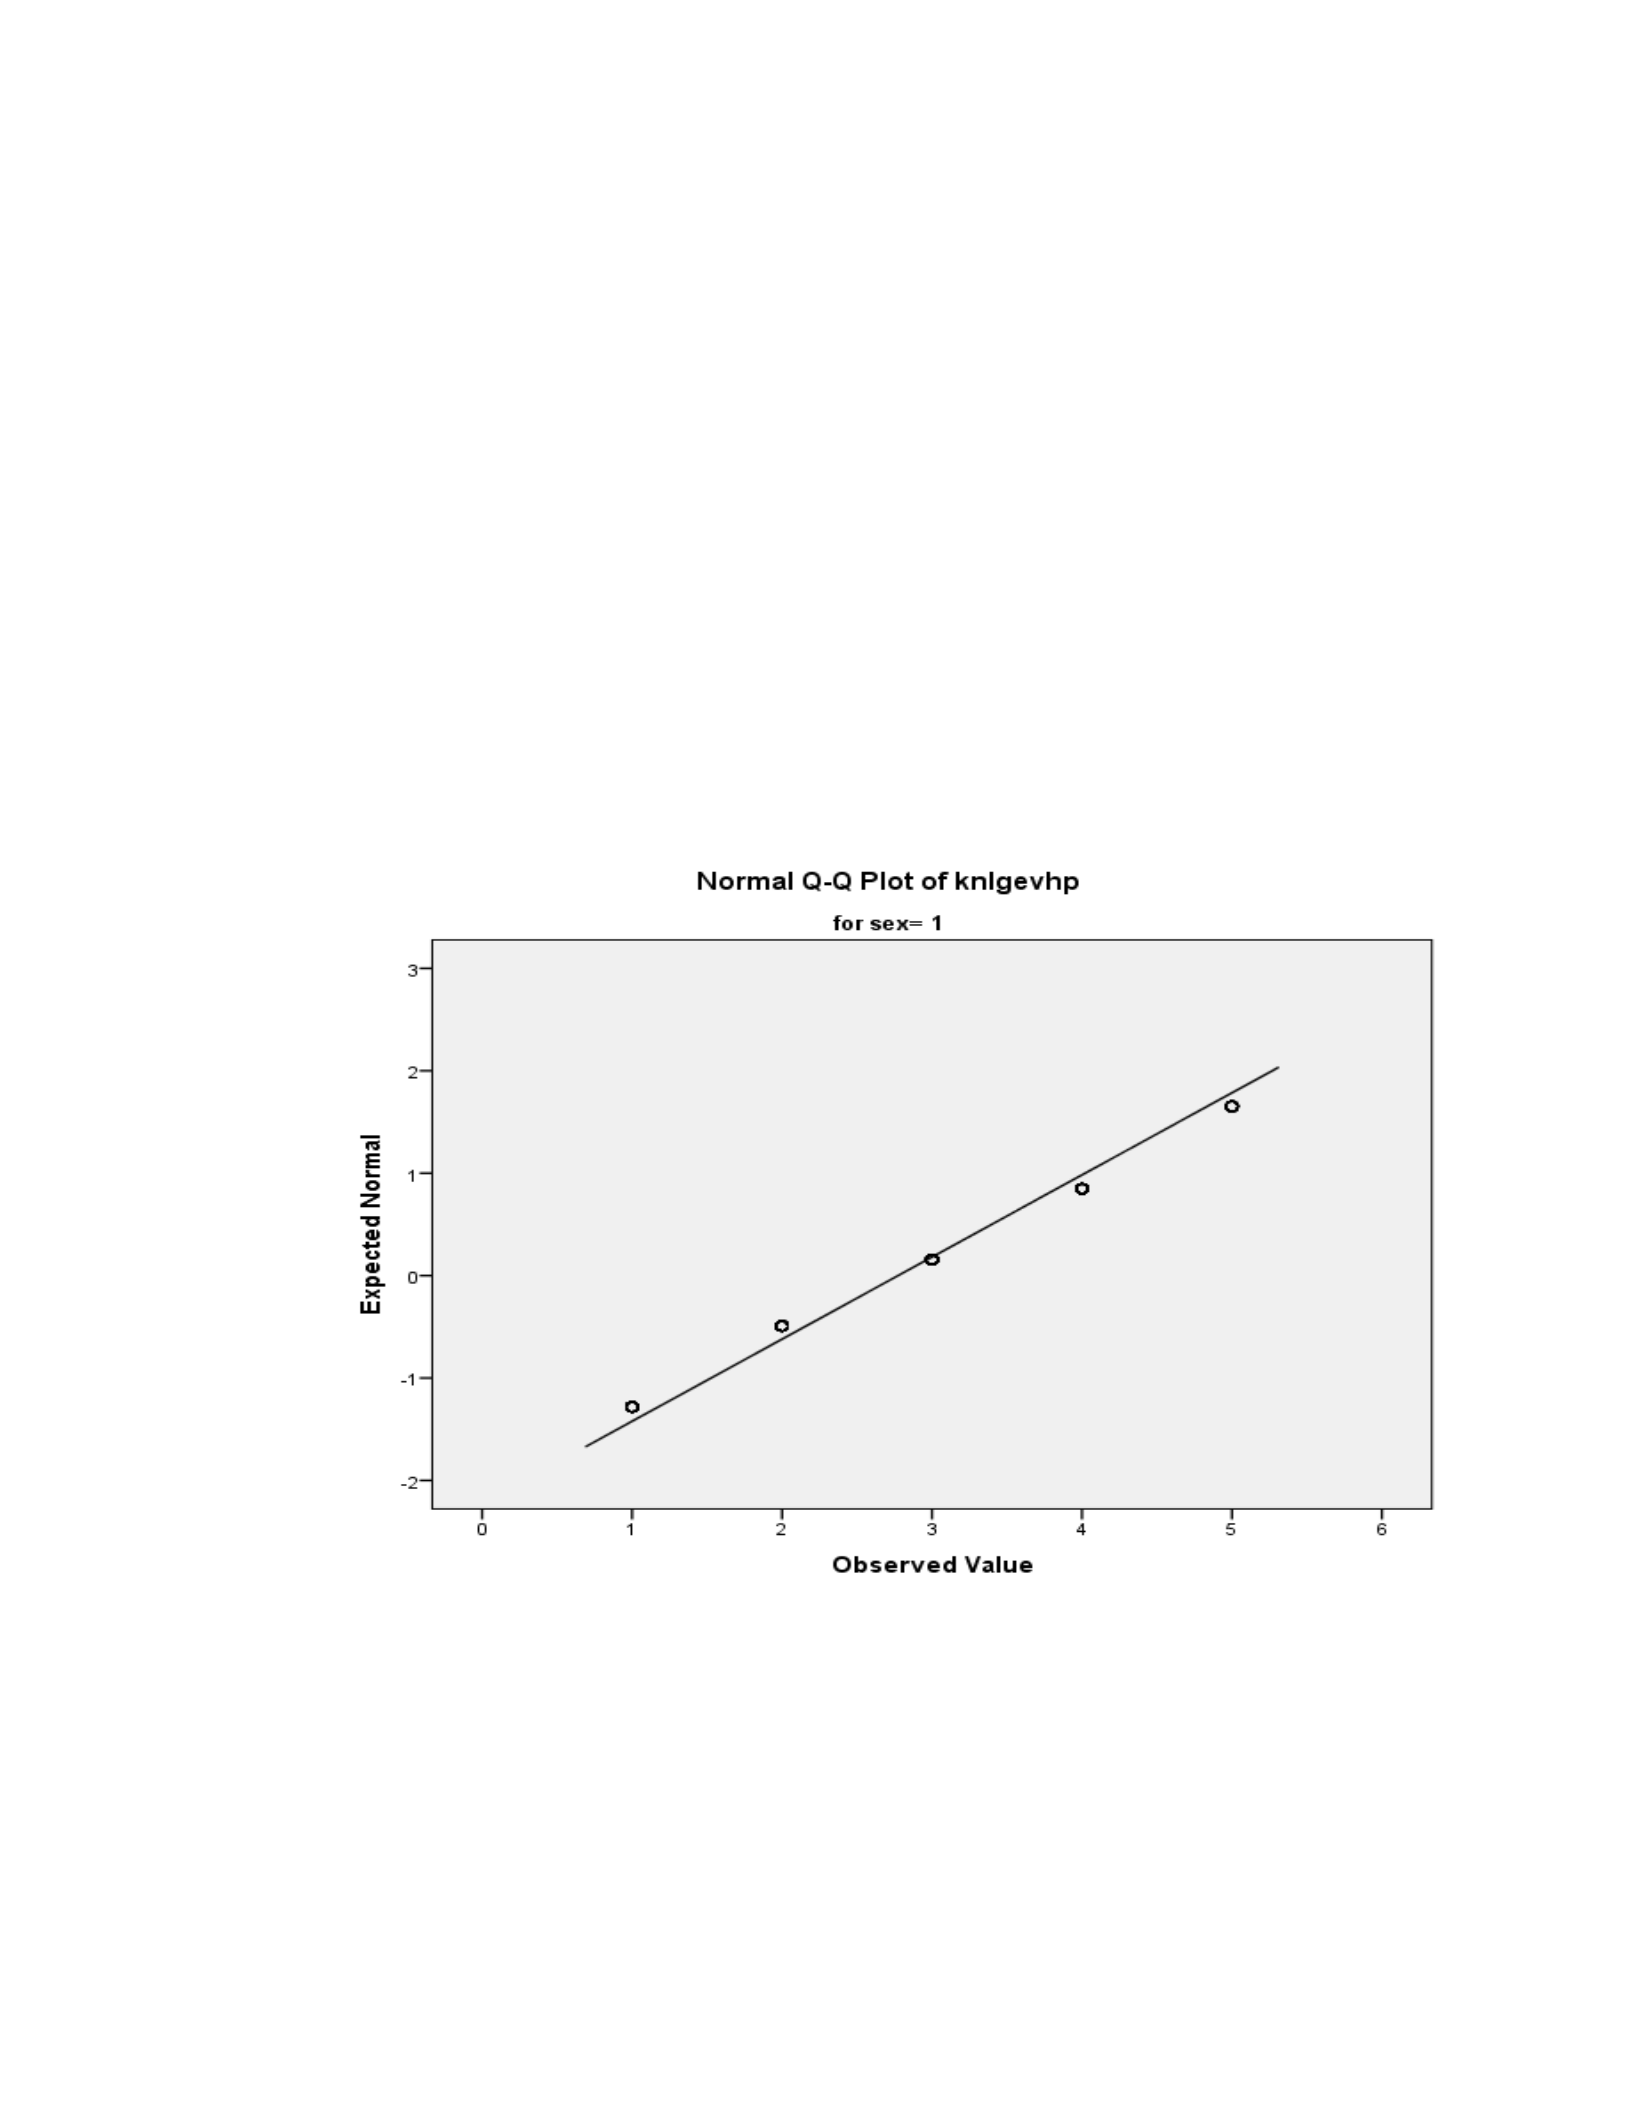
95
non-parametric assumptions, and the hypothesis being tested, the best statistical test was
chosen. The researcher used the online G*Power Data Analysis program to calculate the
power analysis of this potential study. As the power test required a minimum sample size
of 650, no additional power tests were conducted as data was received from 861
participants. The normality and homoscedasticity of the data were measured to determine
if a more appropriate test should be used. The results of each specific test will then be
interpreted and presented. Results will be presented by research question.
Figure 3. Diagram showing the Normal Q-Q Plot for variable knowledge for males
96
Figure 4. Diagram showing the Normal Q-Q Plot for variable knowledge for females.
Knowledge in evaluating health care policies and how they affect PCP practices
were normally distributed for both males and females, as assessed by visual inspection of
Normal Q-Q Plots (Figures 3 and 4). Additional Normal Q-Q Plots were performed for
PCP interest in influencing policies as well as the satisfaction with the impact legislation
has on PCP practices, and as assessed by visual inspection of Normal Q-Q Plots, the data
were normally distributed for both males and females.
Results
The survey was mailed to 1,050 potential participants and the researcher’s
contact information was provided if further clarification was needed. No participant

97
called for clarification. Each survey mailing contained a self-addressed stamped envelope
stamp envelope addressed to designated post office box to return each completed survey.
After each survey response was opened, the return envelope was shredded. All responses
from each of the 861 surveys were entered into the IBM SPSS Statistics 21 software
program which was used to analyze the quantitative data. Participants were informed that
all surveys were anonymous and the information would be kept confidential. Once the
survey responses were entered into SPSS, the data codes and responses were checked
twice to ensure that the information entered was accurate.
In Chapter 3, it was stated that multiple ANOVA tests would be used for the
quantitative analysis based on the variables used in the survey. Pearson’s chi-square tests
were also performed on different variables in selected survey questions. According to
Munro (2005), chi-square analysis should be used to test variables that are categorical,
have frequency data, independent of each other, and have an adequate sample size. The
questions related to the knowledge, interests, and satisfaction of health legislation were
analyzed with the one-way ANOVA tests; once it was determined that the data fit all the
underlying assumptions provided including normality and homoscedasticity. ANOVA
tests were used for questions that used continuous variables, and response choices using
several 5-point Likert scales.
A Levene’s test was performed for each ANOVA test. The Levene's test operates
in the same way as most inferential statistical tests (Agresti, 2012). In this case, it
calculates a statistic which is compared to an F-distribution, with the p-value obtained
indicating the evidence against the null hypothesis (Agresti, 2012). Therefore, a

98
statistically significant result indicates that we should accept the alternative hypothesis,
which is that the population variances are not equal. As such, we usually hope to find that
the test is not statistically significant and we have equal variances (Agresti, 2012).
Due to the types of questions being analyzed for the research questions, non-
parametric tests including the Kruskal-Wallis H test and Spearman’s rank correlation
were also used in the analysis for Research Question 1 (RQ1). Correlation statistics were
used to assess relationships from multiple variables, and were also used to describe the
relationship between those variables. The Pearson’s chi- square test was used to analyze
selected questions from the survey to assess the impact legislation has on the satisfaction
of PCP as well as the hours PCP work each week. Comparisons will be made between
genders on the knowledge, satisfaction, and participation in the health care legislation
process.
Survey questions using a Likert scale for responses were analyzed using Analysis
of Variance tests. Munro (2005) stated that one way ANOVA tests should be used with one
categorical independent variable that has two or more levels and one continuous
dependent variable. A Scheffe’s test was used in the ANOVA Post-Hoc analysis for
multiple comparisons of the differences in means. For ANOVA results obtained with
significance level less than 0.05, the Scheffe’s test result will be highlighted. The
Scheffe’s test was chosen as it is considered to be one of the most flexible and
conservative post-hoc test procedures to analyze the results of the one-way ANOVA tests
when the decision is to reject the null hypothesis (Bergman, 2008). For those cases where
the data fails the assumptions of the one-way ANOVA tests, a Kruskall–Wallis H test

99
was used once the data did not meet the normality assumption of the one-way ANOVA
test (Bergman, 2008).
The Kruskal-Wallis H test is a non-parametric statistical analysis that provides
information similar to that obtained utilizing one way analysis of variance (ANOVA)
technique (Secomb & Smith, 2011). Like the ANOVA, the Kruskal-Wallis H test
examines the equality of population means across three or more populations or groups.
Unlike the ANOVA, the Kruskal-Wallis H test does not require a normal distribution nor
does it presume equal variance among the distributions that are being compared. Because
the intent of the study was to examine more than three independent groups, the Kruskal-
Wallis H test was more appropriate than the Mann-Whitney U test that permits testing of
only two samples (Bazeley, 2009).
These different tests were used in combination to answer all
research
questions.
Multiple-choice questions were analyzed using a chi-square test, and in some cases,
responses were summarized and presented using frequency data in the form of charts
and tables. Likert-scale questions were analyzed using ANOVA. Independent variables
used in this study were knowledge in evaluating health care legislation, race, and gender of
survey participants, as well as PCP satisfaction of the impact of legislation on their
practices. Dependent variable used was availability of PCP using the variable, number of
hours worked by PCP. This study involved using testing the following null hypothesis:
1. There is no significant relationship between health access legislation and
the availability of primary care providers to deliver services.

100
Research Question 1 was answered primarily with the survey questions. An alpha
level of .05 was used for all ANOVA tests. Each survey question was analyzed separately.
This section includes a description of the findings of the quantitative analysis. The
findings are reported utilizing the research question of this study.
To answer Research Question 1, “What is the relationship between health access
legislation and the availability of primary care providers” the survey questions were
analyzed. The researcher analyzed the relationship between variables to identify factors
that impact the number of hours PCP work each week.
The question “How knowledgeable are you in evaluating health policies that
impact your practice” resulted in an F ratio of F (4,856) = 4.144, p = .002. The null
hypothesis for this research question is that there is no difference in the mean knowledge
of legislation of PCP who work fewer than 20 hours, 21-30, 31-40, 41-50, and greater
than 50 hours each week. At the alpha level of .05, there is enough evidence to conclude
there were differences in the mean knowledge in evaluating health policies between PCP
who work different hours each week. However, there was not homogeneity of variances,
as assessed by Levene's test for equality of variances (p = .019).
A Kruskall-Wallis H test was then conducted to determine if there were
differences in the mean knowledge of PCP who work the above mentioned hours each
week. Distributions of hours were similar for all groups, as assessed by visual inspection
of a boxplot. Calculation of the Kruskal-Wallis H test statistics resulted in Χ2K-W =
13.473, df = 4, p =0.009. The X2K-W value that was calculated as 13.473 and the p value
of 0.009 indicated that there is a statistically significant difference in the mean knowledge of

101
legislation for PCP who work fewer than 20 hours, 21-30, 31-40, 41-50, and greater than 50
hours each week.
The analysis of the question “How interested are you in influencing health access
policies” resulted in an F ratio of F (4, 856) = 2.003, p = .092. There was homogeneity of
variances, as assessed by Levene's test for equality of variances (p = .073). At the alpha
level of .05, there is enough evidence to conclude there were no differences in the mean
interest in influencing health policies for PCP who work fewer than 20 hours, 20-30, 30-40,
40-50, and greater than 50 hours each week.
The analysis of the question “How important are primary care providers’ input in
developing health policies” resulted in an F ratio of
F (2, 858)
= 3.426, p = .033. At the
alpha level of .05, there is enough evidence to conclude there is a relationship between
physician availability and including PCP input in the development of health care policies.
There was homogeneity of variances, as assessed by Levene's test for equality of
variances (p = .196). The Scheffe’s test results showed with α = 0.05, we can conclude
that the mean provider input is larger with PCP who work 30 – 40 hours each week than
with those who work 40 – 50 hours each week. Also, the mean provider input is larger
with PCP who work less than 20 hours each week than with PCP who work greater than
60 hours each week.
The analysis of the question “Please check any of the following that apply to your
involvement in health policy in the past two years” was done using a one-way ANOVA
test. A one-way ANOVA was conducted to determine if the PCP’ involvement in
changing health policy was different for PCP who were employed in public/government

102
entities, private entities, owner operated practices, or other types of employment settings.
Participants were classified into 4 groups: public (1) (n= 192), private (2) (n= 235),
owner or partner (3) (n= 199), and educator (4) (n= 235). There were no outliers, as
assessed by boxplot; data was normally distributed for each group, and there was
homogeneity of variances, as assessed by Levene's test of homogeneity of variances (p =
.987). The differences between these PCP practicing in different areas groups was not
statistically different, F (3, 857) = 2.108, p = .098.
The question “Please check any of the following that apply to your involvement
in health policy in the past two years” was further analyzed using another one-way
ANOVA test. This resulted in an F ratio of F (3, 857) = 2.775, p = .040. At the alpha
level of .05, there is enough evidence to conclude there was a relationship between
physician availability and their involvement in changing health policy within the past two years.
There was homogeneity of variances, as assessed by Levene's test for equality of
variances (p = .425). The Scheffe’s test results show that with α = 0.05, we can conclude
that the mean involvement in health policy in the past two years is larger with PCP
working between 40 and 50 hours each week than with those working less than 20 hours
per week.
The researcher analyzed whether there was a difference in male and female PCP
knowledge in evaluating health policies that affect their practice. A two-way between-
groups ANOVA test was used to analyze the question “How knowledgeable are you in
evaluating health policies that affect your practice’ was used. There was a statistically

103
significant difference in knowledge level scores for males and females, F(1, 851) =
23.924, p < .005, partial η2 = .17
A Likert scale of 1 through 5 representing very dissatisfied (1) to very satisfied (5)
was used to obtain responses for the survey question “How satisfied are you with the
impact health legislation has on your practice (Circle one)”. Table 8 illustrates the
responses collected for this question.

104
Table 8
Responses to Survey Question 5, Satisfaction with the Impact of Legislation on PCP
Practices
Rating Frequency (N = 861) %
1(Very Dissatisfied) 384 44.6
2 344 40.0
3 133 15.4
4 0 0
5 (Very Satisfied) 0 0
Total 861 100
A one-way ANOVA was conducted to analyze PCP satisfaction of the impact
health legislation has on the practices of PCP was different for providers located in rural,
urban, and sub-urban areas. Participants were classified into 3 groups: rural (n=384),
urban (n=344), and sub-urban (n=133). There were no outliers, as assessed by boxplot;
data was normally distributed for each group, and there was homogeneity of variances, as
assessed by Levene's test of homogeneity of variances (p = .146). The differences
between these PCP practicing in different areas groups was statistically different, F (2,
858) = 10.608, p < .005. The Scheffe’s test results showed with α = 0.05, we can
conclude that the mean satisfaction is larger with PCP practicing in urban areas than with
those who are located in sub-urban areas. Also, the mean provider input is larger with
PCP who work in rural areas than compared to those working in urban areas.
Another one-way ANOVA test was conducted to analyze PCP satisfaction of the
impact health legislation has on the practices of PCP was different for providers based on
the hours worked each week. There was homogeneity of variances, as assessed by

105
Levene's test of homogeneity of variances (p = .058). The differences between these PCP
practicing in different areas groups was statistically different, F (4, 856) = 2.959, p =
.019. The Scheffe’s test results showed with α = 0.05, we can conclude that the mean
satisfaction is larger with PCP who work more than 60 hours each week than with those
work less than 20 hours each week. Also, the mean satisfaction is larger with PCP who
work between 40 - 50 hours each week than with those work less than 20 - 30 each week.
The researcher also analyzed whether there was a difference in male and female
PCP satisfaction on the impact of legislation on their practice. A two-way between-
groups ANOVA test was used to analyze the question. There was a significant difference
in satisfaction score for males and females, F(1, 851) = 2.710, p < .005, partial η2 = .220.
Table 9 shows the questions analyzed using a one way ANOVA and an overview
of the findings for Research Question 1 on the primary care providers views on the
impact of health legislation on their practices of PCP based on the hours worked each
week.

106
Table 9
Results
of ANOVA
Test
for
Mean
Differences Among the Average Hours worked each week by
Primary Care Providers Respondents
Analysis
Question
ANOVA
Results
Participants (Avg
Hours worked per
week)
How knowledgeable are you in evaluating
health policies that impact your practice
p = .002* 0 - 20 (n = 189)
21 - 30 (n=230
30 - 40 (n=245)
40 - 60 (n=157)
> 60 (n = 40)
How interested are you in influencing
health access policies
p = .092 0 - 20 (n = 189)
21 - 30 (n=230
30 - 40 (n=245)
40 - 60 (n=157)
> 60 (n = 40)
How important are primary care providers’
input in developing health policies
p = .033* 0 - 20 (n = 189)
21 - 30 (n=230
30 - 40 (n=245)
40 - 60 (n=157)
> 60 (n = 40)
How satisfied are you with the impact
health legislation has on your practice
p = .019* 0 - 20 (n = 189)
21 - 30 (n=230
30 - 40 (n=245)
40 - 60 (n=157)
> 60 (n = 40)
Please check any of the following that
apply to your involvement in health policy
in the past two years
p = .040* 0 - 20 (n = 189)
21 - 30 (n=230
30 - 40 (n=245)
40 - 60 (n=157)
> 60 (n = 40)

107
To what extent do these restrictions affect
the number of patients that you see daily
p = .584 0 - 20 (n = 189)
21 - 30 (n=230
30 - 40 (n=245)
40 - 60 (n=157)
> 60 (n = 40)
Note. *indicates a significant relationship
Table 10 shows the responses for survey question 6, “Place a check next to what
you believe restrict the scope of your services the most”. Twenty-eight percent (n =241)
of participants responded that uncertainty/changes in health care reform restricted the
scope of the services they offered. Another 24% (n = 207) indicated non-clinical/administrative
paperwork requirements restricted the scope of the services that they provide. Dealing with
Medicare/Medicaid/Other government regulations was identified by 19% (n = 160) of
respondents as restricting the scope of services. Reimbursement issues, lack of clinical
autonomy, and managed care regulations were the other factors respondents identified that
restricted the scope of their services.
Table 10. Factors that Restrict the Scope of Services Provided by PCP
Frequency (N = 861) Percent
Reimbursement issues 131 15.2
Lack of clinical autonomy 90 10.5
Medicare/Medicaid/Govt reg 160 18.6
Non-clinical duties 207 24.0
Uncertainties 241 28.0
Managed care regulations 32 3.7
Increasing training costs 0 0
Other 0 0
Total 861 100

108
One hundred and ninety two respondents stated that they were not involved in
health policy development within the past two years. Approximately 27% (n = 235)
respondents stated that they were involved through their professional bodies. Ninety-five
percent (n = 223) of these respondents (n = 223) who were involved in changing health
policy within the past two years through their professional organizations identified
themselves as members of the American Medical Association. Two hundred participants
were health policy advocates. Sixty-five percent (n = 130) of the American Osteopathic
Association respondents considered themselves as health policy advocates and were
involved in changing health policy in the past two years.
Figure 5 shows the frequencies of the responses to Survey question number 9,
“What do you think are barriers in developing more effective health policies”. Lack of
time and uncertain outcome, were identified as the leading barriers in developing health
policies. Other notable barriers were frustration with the policymaking process, political
influences, lack of money or resources, and the possibility that the policy will not make a
difference in health care delivery.
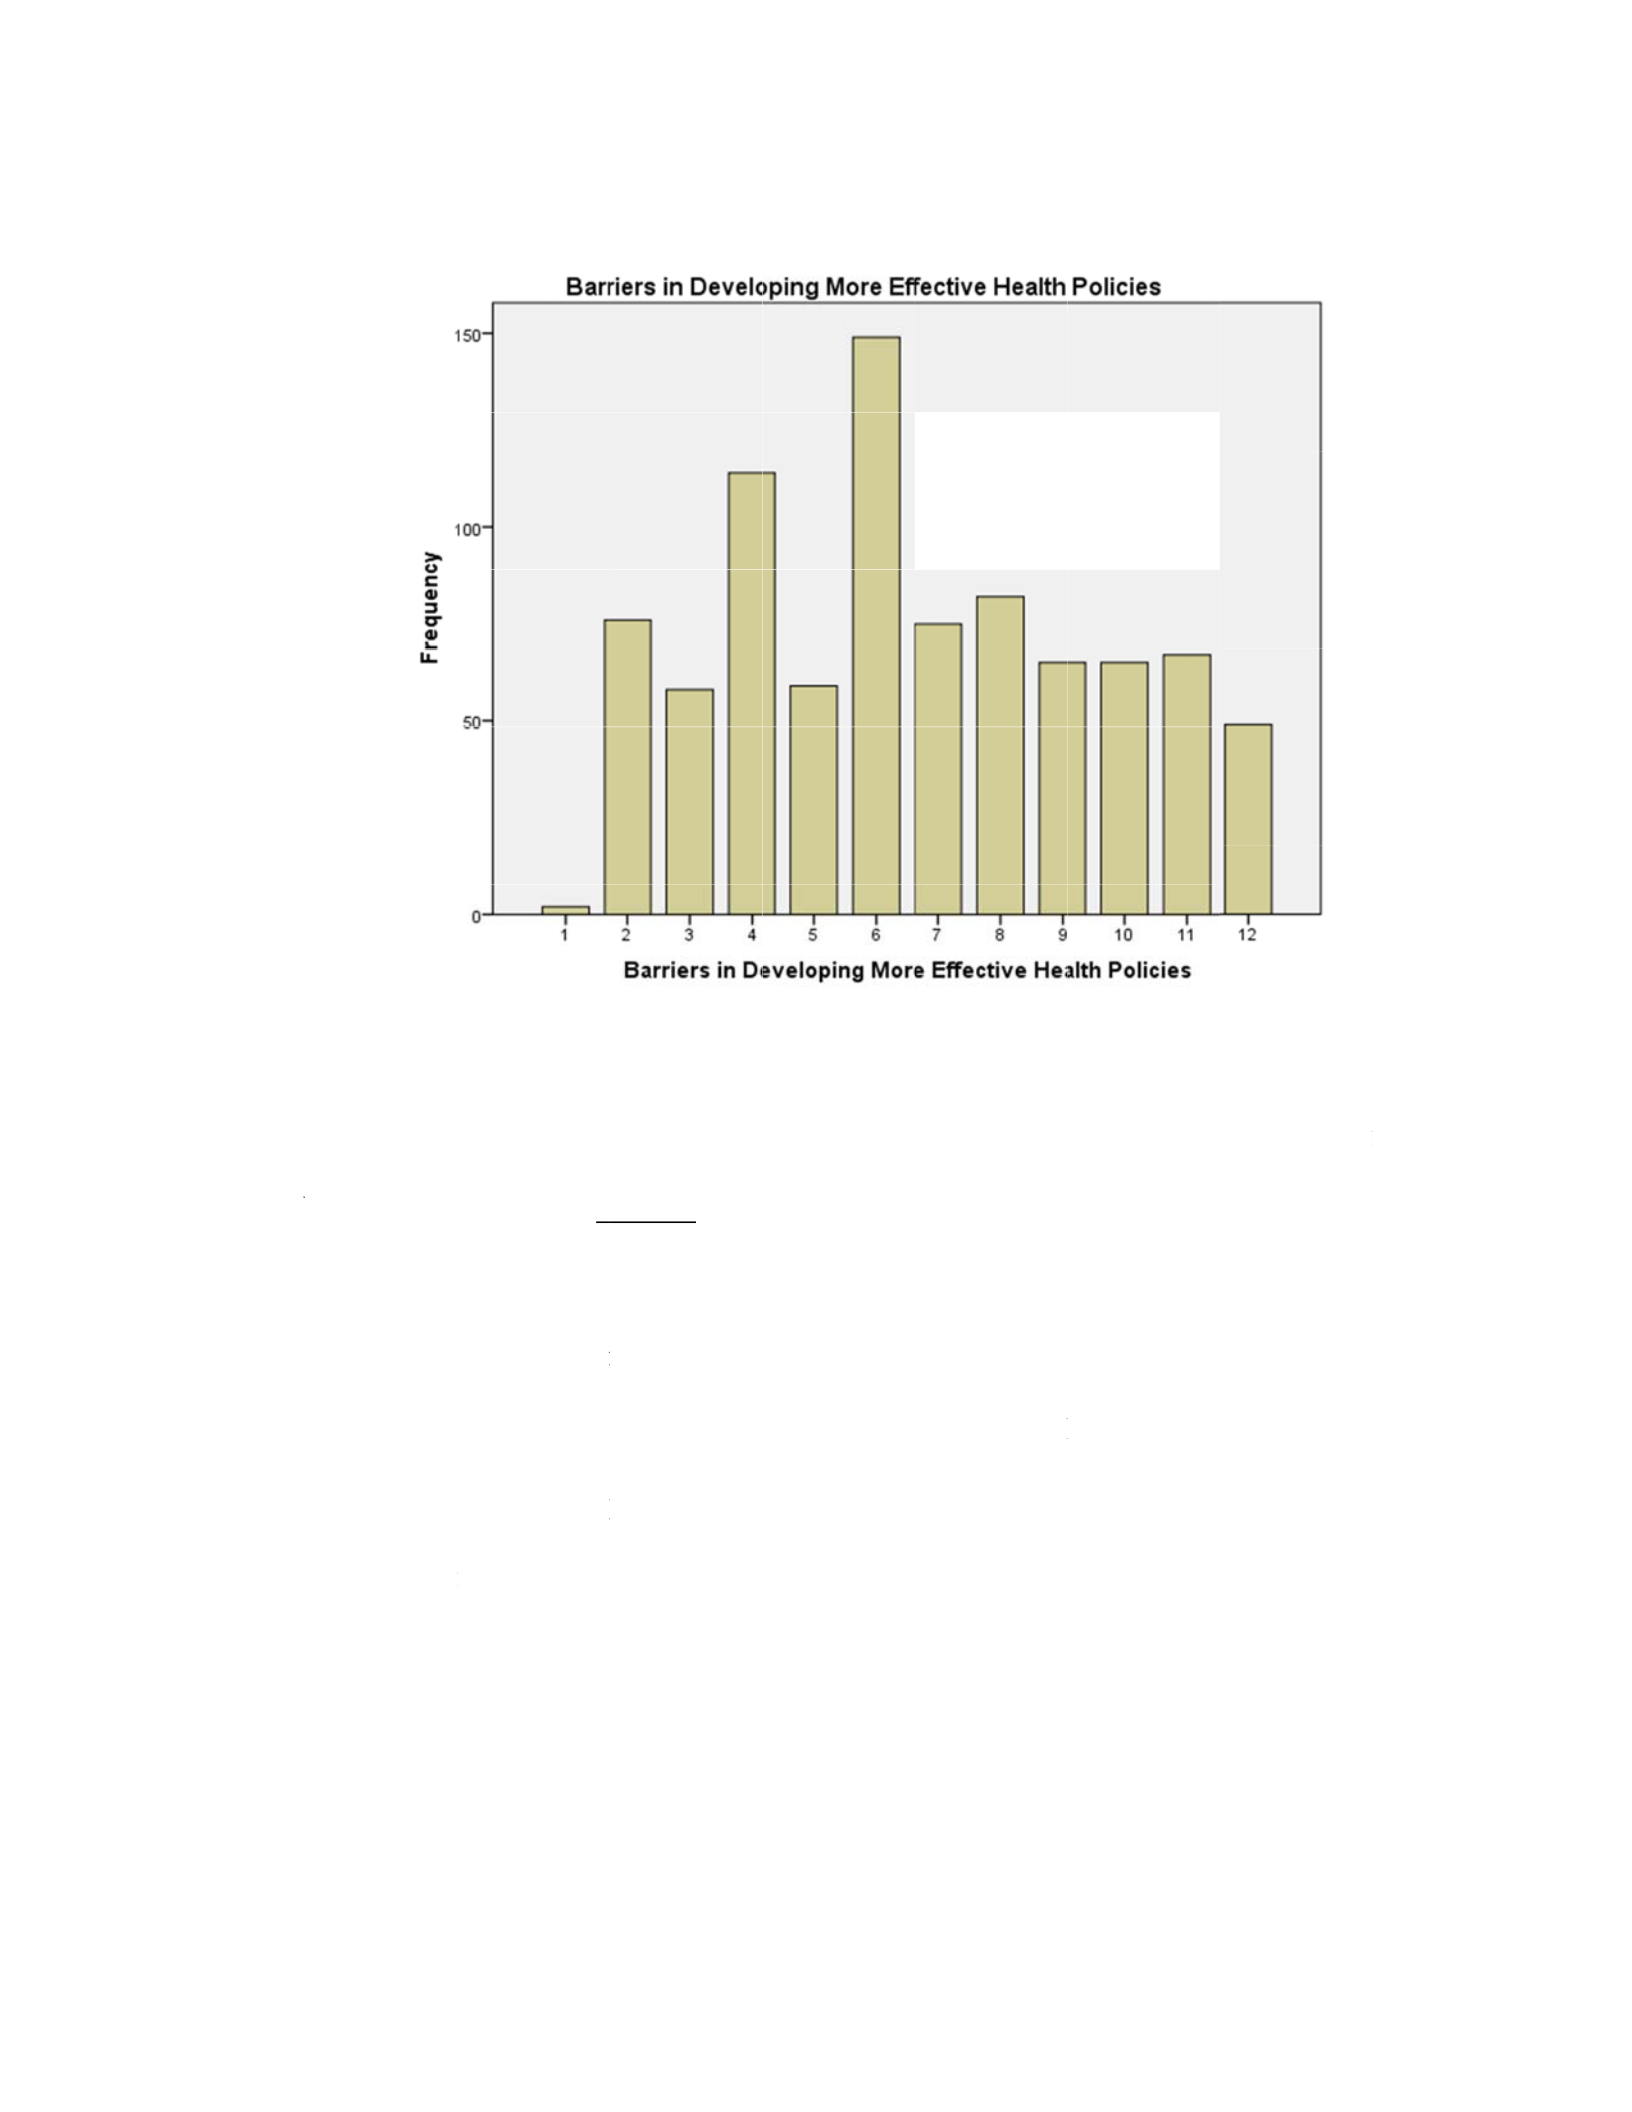
F
“
W
H
b
a
n
P
a
F
igure 5. Ba
r
Simil
a
W
hat do yo
u
H
CPs compl
y
enefit of po
l
n
d improvi
n
CP identifi
e
difference i
n
r
riers in De
v
a
rly, Figure
u
think are
b
y
with laws
w
l
icy develop
m
n
g health car
e
e
d. Other res
p
n
patients’ l
i
v
eloping Mo
r
6 shows the
b
enefits of h
e
w
as identifi
e
m
ent and e
v
e
quality wi
t
p
onses incl
u
i
ves.
r
e Effective
leading be
n
e
alth policy
d
e
d by 18% (
n
v
aluation. R
e
t
h 12% (n =
u
ded, creati
n
Health Poli
c
n
efits partici
p
developme
n
n
= 157) of
r
e
ducing dis
p
104) were t
h
n
g uniform s
t
c
ies
p
ants list fo
r
n
t and evalu
a
r
espondents
p
arities with
h
e other lea
d
t
andard of c
r
the questio
n
a
tion”. Havi
n
as the great
13% (n = 1
1
d
ing benefit
s
are, and ma
k
109
n
n
g
est
1
1)
s
k
ing
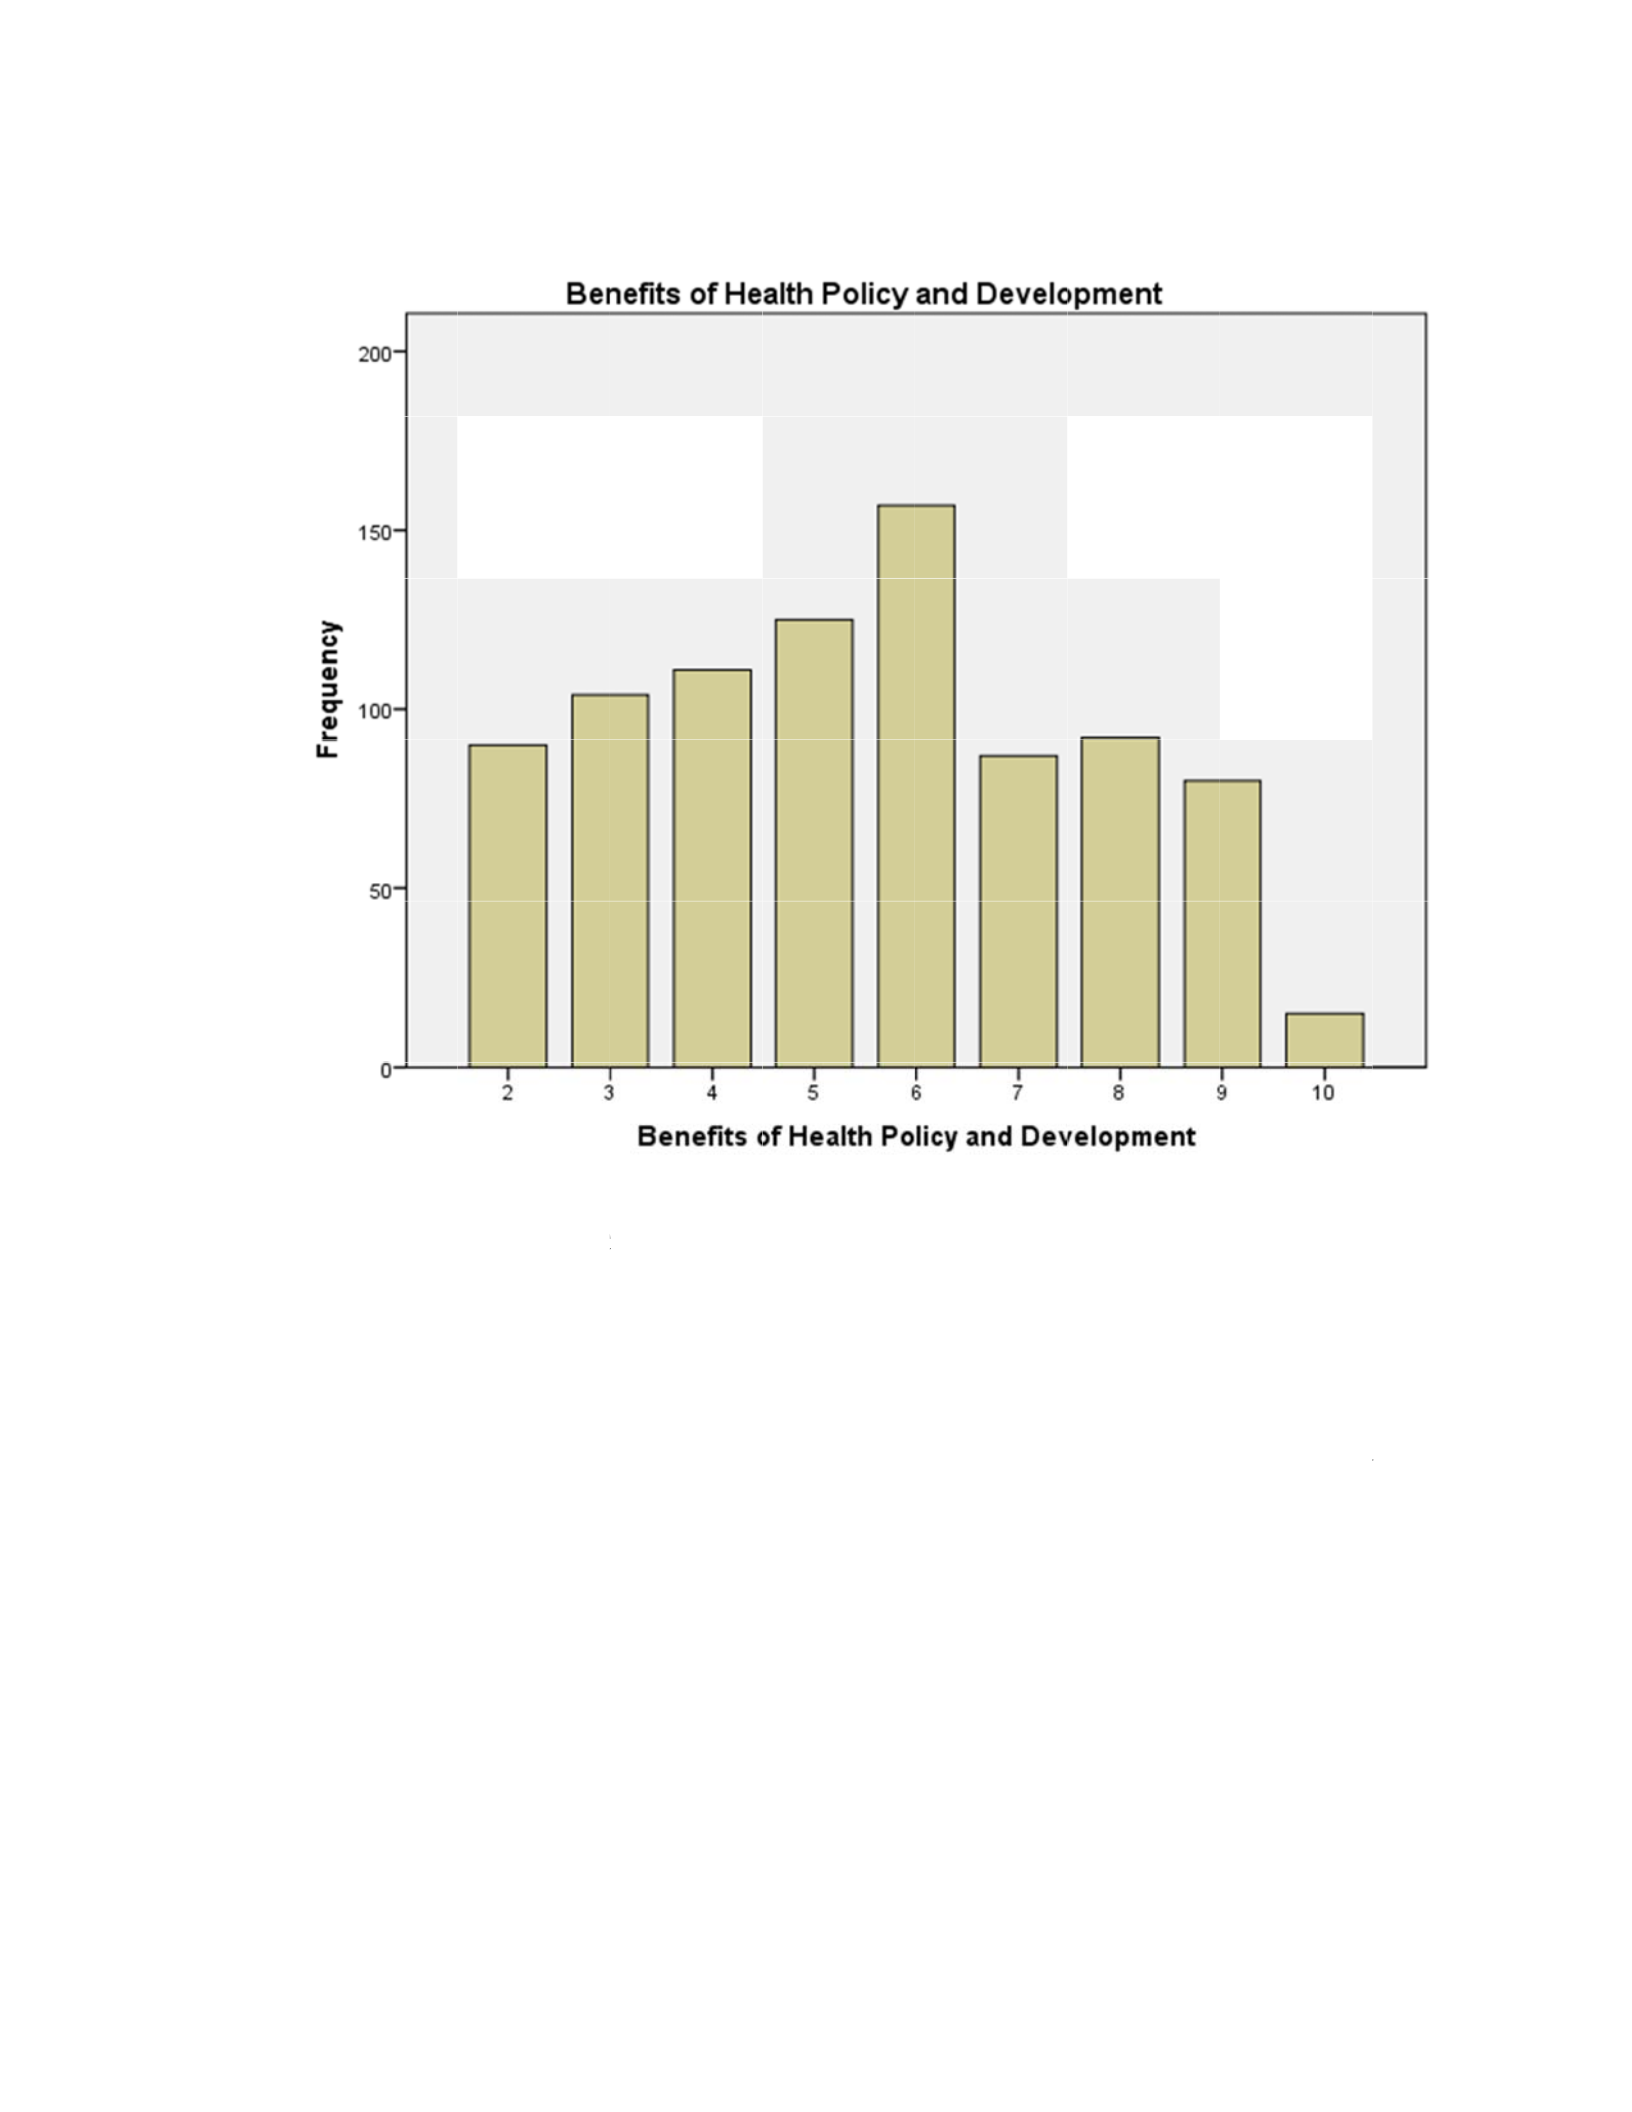
F
e
v
d
p
A
f
a
d
F
igure 6. Fa
c
v
aluation.
Surv
e
i
ssatisfactio
n
ercent (n =
2
A
dministrati
v
a
ctor contri
b
ecreasing a
u
c
tors that P
C
y Question
n
n
as a PCP”
2
55) were d
i
v
e hassles /
n
b
uting to the
i
u
tonomy we
r
C
P identify a
s
n
umber 11
“
had all 861
i
ssatisfied w
n
on-clinical
i
r disaffecti
o
r
e the other
l
s
benefits o
f
“
Which of t
h
respondent
i
ith the low
r
paperwork
w
o
n. Fee-for s
l
eading fact
o
f
health poli
c
h
e following
i
dentify one
r
eimbursem
e
w
ere identif
i
s
ervice reim
b
o
rs. Ten res
p
c
y develop
m
contributes
dissatisfact
i
e
nt rates for
i
ed as the se
b
ursement r
e
p
ondents sel
m
ent and
to your
i
on. Twent
y
their servic
e
cond highes
e
quirements
,
ected other
f
110
y
-nine
e
s.
t
,
and
f
or
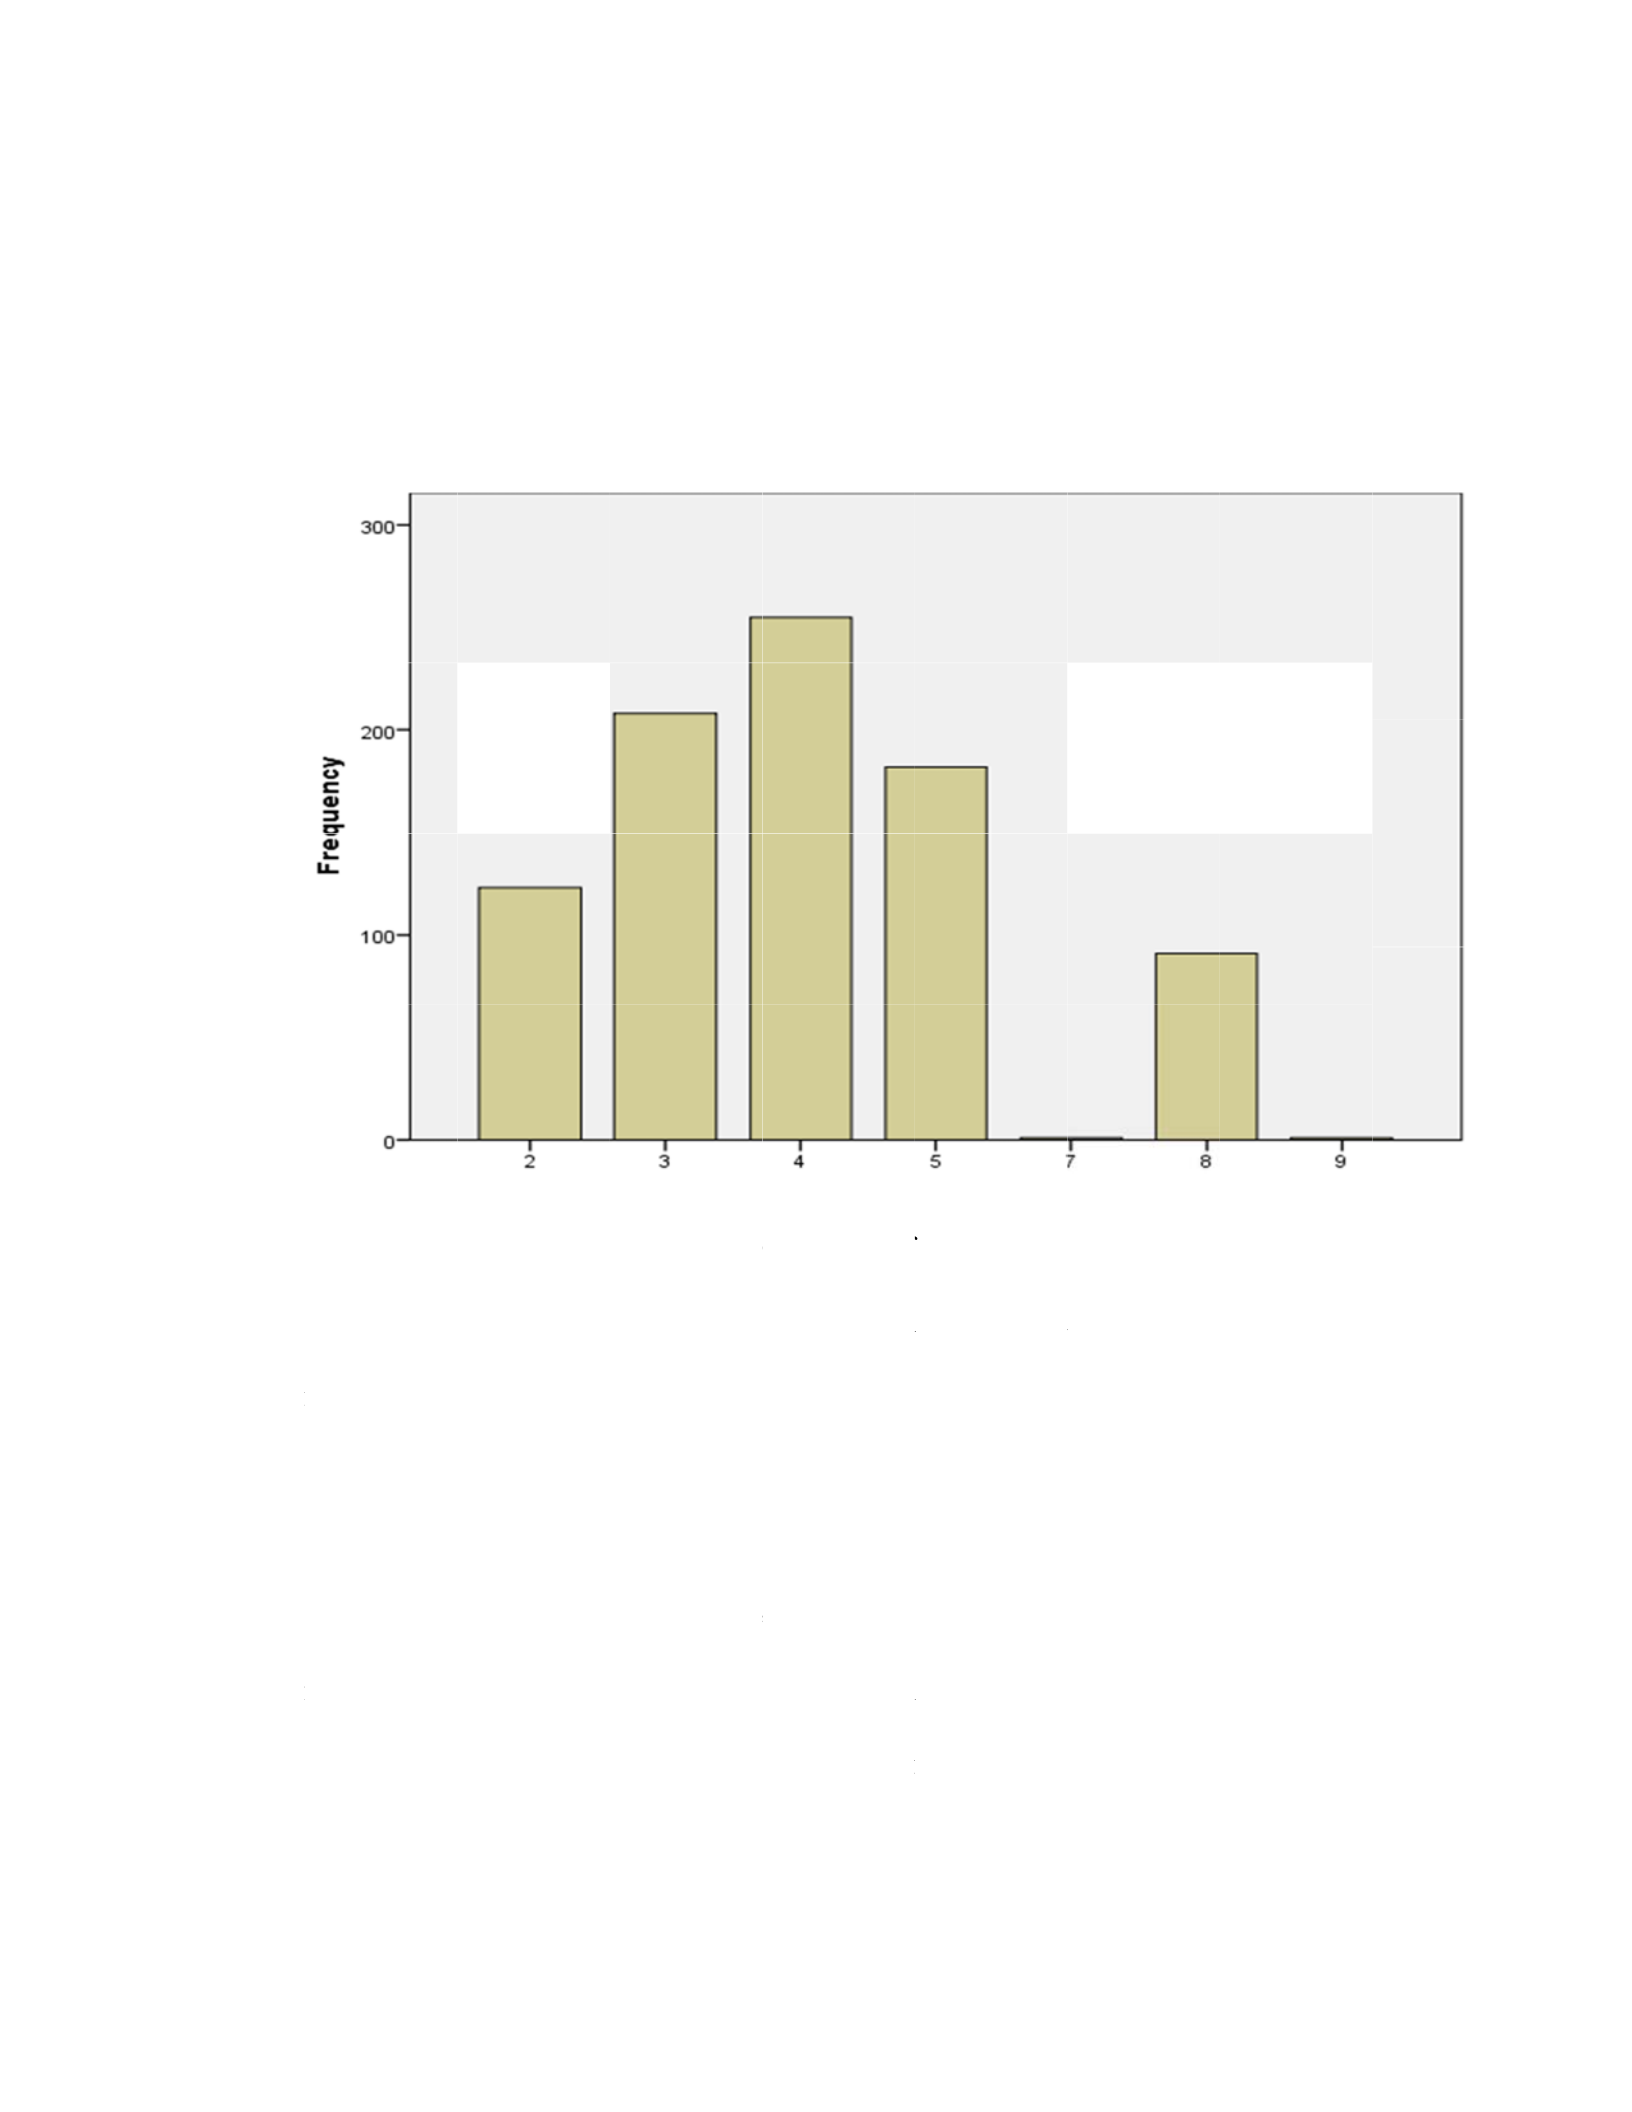
t
h
s
t
F
o
r
A
t
h
t
o
p
r
t
r
h
eir choices.
t
artup costs,
F
igure 7. Fa
c
Forty
-
r
training o
n
A
ffordable C
h
e responde
n
o
implemen
t
r
actices. Th
i
r
aining for
w
Among the
and the hig
h
c
tors that co
n
-
two percen
t
n
how to im
p
are Act (PP
A
n
ts stated th
a
and analyz
e
i
rty-five per
c
w
orkshops, 2
list of facto
h
provider t
o
n
tribute to P
C
t
(n = 371)
o
p
lement and
A
CA) will
h
a
t they did n
e
this new l
e
c
ent (n = 12
7
9% (n = 10
5
rs listed as
“
o
patient rat
i
C
P dissatis
f
a
o
f responden
analyze the
h
ave on thei
r
ot receive a
d
e
gislation an
d
7
) of respon
5
) received i
n
“
Other” wer
e
i
o.
f
action.
n
ts stated tha
effect the P
a
r
practices.
M
d
equate trai
n
d
the impac
t
n
dents recei
v
nformation
f
e
financial
d
a
t they recei
v
a
tient Prote
c
M
ore than h
a
n
ing or info
r
t
it will imp
a
v
ed this info
r
f
or professi
o
d
ebt, practic
e
v
ed informa
t
c
tion and
a
lf (n = 498)
r
mation on
h
a
ct their
r
mation or
o
nal
111
e
t
ion
of
h
ow

112
organizations that they belonged to, while 28% (n = 101) received in-the-job training on
how this new legislation will impact their practices.
A Pearson correlation was run to assess the correlation between satisfaction of the
impact of health legislation and employment setting, and satisfaction of the impact of
health legislation and the geographical location of practices. Preliminary analyses showed
the relationship to be linear with both variables normally distributed, as assessed by
Shapiro-Wilk test (p > .05), and there were no outliers. Using the guidelines provided by
Agretsi (2012) where the absolute value 0.1 < | r | < 0.3, there was a small positive
correlation between satisfaction and employment setting, r(859) = .106, p = .002. There
was a negative correlation between satisfaction and geographical location, r(859) = -.019,
p > .05. Since the p-value is greater than .05, then we cannot conclude that the
correlation between satisfaction and geographical location of practices is different from 0.
Another Spearman’s rank-order correlation test was done to assess the correlation
between satisfaction and the extent to which these affect the number of patients PCP see
each week. While there was a negative correlation coefficient between satisfaction and
the extent to which this affects the number of patients seen, the p-value again was greater
than .05.
A Spearman's rank-order correlation was run to assess the relationship between
satisfaction of the impact of legislation on PCP practices and age of PCP. Preliminary
analysis showed the relationship to be monotonic, as assessed by visual inspection of a
scatterplot. There was a negative correlation between age and satisfaction, rs = -.101, p <
.0005.

113
A chi-square test for association was conducted between gender and PCP hours
worked each week in order to assess if there was a relationship between PCP genders and
hours worked each week. All expected cell frequencies were greater than five. There was
a statistically significant association between gender and average hours worked each
week, χ2(16, N=861) = 34.813, p = .004.
Another chi-square test for association was conducted on satisfaction and
geographical location of practices. All expected cell frequencies were greater than five.
There was a statistically significant association between satisfaction and rural, urban, and
suburban practice locations, χ2(4, N = 861) = 22.712, p <.005.
A chi-square test for association was conducted between PCP hours worked each
week and satisfaction on the impact in evaluating health policies. All expected cell
frequencies were greater than five. There was a statistically significant association
between and preference for performing competitive sport, χ2(8, N = 861) = 18.392, p =
.018. There was a statistically significant association between gender and average hours
worked each week, χ2(4, N = 861) = 34.813, p = .004.
Qualitative Data
A
n
a
lysis
The concepts and ideas of the study’s respondents must be formulated to show
collective experience. Researchers can learn the lived experiences of participants when
they carefully listen to the responses each participant provides (Creswell & Plano-Clark,
2007). The general information from the responses will then be tied together to obtain an
in-depth understanding of the perceptions of PCP (Creswell, 2013). This provides the
advantage of examining individual experiences by providing a description of what the

114
shared experiences of the participants are (Creswell, 2013). By reviewing the transcripts of
the interview sessions, qualitative data analysis will highlight significant statements
(Creswell, 2013). Themes were derived from these significant statements which will
allow the research to be described through a composite description (Creswell, 2013).
The themes were derived using primarily manual coding. As a secondary check,
the qualitative software Computer Assisted Qualitative Data Analysis (CAQDAS). These
themes generated from CAQDAS will then be matched against the themes derived from
the manual coding process to triangulate the qualitative data with the quantitative data.
Telephone interviews sessions were conducted by the researcher with PCP who
returned the Consent Form for Participants / Invitation to Participate (Appendix B).
These interviews were digitally recorded. Participants were informed that while their
answers were not anonymous, they would be kept confidential. The researcher informed
all participants that all information shared in the interview session would stay in the
session and information shared would not be tied directly to each participant. Following
the interview, participants were told that they will be provided with a written transcript of
the interview, and encouraged to review and provide any clarifications or additional
information to provide an accurate reflection of their statements. All transcriptions from the
interview sessions have been kept in a secured location.
Each interview was digitally recorded, transcribed, and analyzed from the original
transcriptions. This method was used to provide credibility of the data analysis. Each
transcription was reviewed by the participants for significant statements related to

115
knowledge of health access legislation, perception of these legislation, and the
experiences these legislation have on their practices.
The following research questions were used to analyze these qualitative data:
1. What are primary care providers’ perceptions regarding reducing
disparities in access?
Survey question 13 was also used to answer this research question along with
the responses from the interview sessions.
Semi-structured telephone interviews were conducted for the qualitative data of
this research study. Once the qualitative data collection was completed, three levels of
coding were used; descriptive coding, topic coding, and analytical coding (Creswell,
2009). The first phase of analysis utilized descriptive coding to review each interview
based on the hours worked by each physician and gender. Themes were identified
after coding responses into categories utilizing topic coding. Finally, analytical
coding was used to place topics into themes. Axial coding was also used to answer
each research question so a response could be identified for a theme. Themes were
used for more than one research question. Inductive reasoning was used to create
subgroups of responses and then develop themes. Each theme was derived from
similar responses across each category of participants. Responses were qualified to
contribute to a theme.
In order to support the development of a theme, only subcategories with two or
more coded responses were used. Coded responses were then organized to show how one
code supports another by placing the coded responses into subcategories (Schutt, 2012).

116
Responses which were coded into subcategories could be used to support more than one
theme. The use of subcategories overlapping in more than one theme also shows how the
concepts of subcategories support each other (Schutt, 2012). Identified themes were also
used to answer both research questions in this research study.
Research Question 1(RQ1) “What is the relationship between health access
legislation and the availability of primary care providers” was answered using the
analysis of all 15 semistructured interviews. The five themes that emerged from this
analysis were: PCP focus more on daily requirements rather than on understanding health
policy; controlling cost, quality or access affect physicians; PCP have little influencing in
affecting policy; lack of interest in increasing supply of PCP; and decreasing PCP
remuneration.
Desc
r
i
p
t
ive
Analysis
Table 11 shows an overview of these themes which are supported by direct quotes
in the thematic analysis overview. The table displays the number of responses from the
semistructured interview participants. The following themes were identified in all PCP
based on the hours each participant stated that they worked each week. The table displays
the number of coded responses supporting each theme. There were a total of 15
participants in the interviews; 4 PCP worked less than 20 hours each week, 3 PCP
worked over 20 hours but less than 30 hours each week, 3 PCP work between 30 and 40
hours each week, 3 PCP worked between 40 and 60 hours each week, and 2 PCP work
more than 60 hours each week.

117
Table 11
Interview Responses and Themes of the Relationship Between Health Legislation and
Primary Care Provider Availability (Hours Worked Each Week) (N = 15)
Themes
<20
21 –
30
30 –
40
40 –
60
>
60
Theme
Total
PCP focus more on daily
requirements rather than on
understanding health policy
4 2 3 0 2 11
Controlling cost, quality or
access affect physicians
3 3 3 3 1 13
PCP have little influencing in
affecting policy
3 2 1 2 0 8
Lack of interest in increasing
supply of PCP
4 3 2 0 2 11
Decreasing PCP remuneration 3 3 3 2 2 13
Thematic Analysis
The first theme for Research Question 1, PCP focus more on daily requirements
rather than on understanding health policies emerged based on discussion on physician
work schedule. Key elements that were used to identify this theme were responses
surrounding time spent on delivering health care services to patients. Each participant
relayed personal experiences on the time spent seeing patients. Eleven PCP mentioned
that PCP focus more on their daily duties rather than understanding how to evaluate the
impact policies have on how they provide care. When asked to define what these daily
duties were; the participants stated overseeing staff, maintaining practice requirements,
participating in health conferences and pharmaceutical seminars, reviewing new studies

118
or clinical trial information, educators at universities and medical schools, and with time
permitting they will oversee the patients referred to them by their support staff. These
PCP stated that they were either partners or owners in health care practices. Four of these
11 providers stated that they hire several physician assistants (PA) and nurse practitioners
(NP) to deliver primary care services and focus more on the daily duties identified above.
The four PCP who did not mention this theme stated that they were employees of health
care facilities.
Through the discussion on expanding the number of actively practicing PCP, the
topic of the PPACA emerged. The theme surrounding improving access, quality and
reducing costs was mentioned by 13 participants. One interesting statement repeated by
multiple participants was the direct relationship improved access, quality and cost
reduction has on the number of hours health care providers work. While the PCP agreed
that they were willing to work more hours, they would prefer less emphasis be placed on
cost reduction and improved quality. One PCP stated “If the PPACA wants us to see
more patients, then we should be able to solely set our rates. You can’t expect us to want
to see more patients when you only reimburse a portion of the true costs, or have
insurance plans that limit how often patients can seek care, or penalize us when patients
do not completely recover”. When asked to expand further, the PCP stated that many of
the patients seen in the practice who obtained through the insurance market place
provide free preventive care services annually. The amounts reimbursed to his practice,
are significantly less than what they received in previous years. In some cases they were
up to seventy five percent less than the amounts received in the past 5 years.

119
Another PCP stated that reducing health care cost is one of the “major reason I
focus more on not seeing patients”. The respondent reason further stated “While I love
the health care profession, I would like to operate a financially successful practice”. The
PCP further stated that “this is basic accounting. Reducing the cost that you can charge
patients will result in lower business income. To add to that, the cost of treatment and
medical equipment are expensive. To be reimbursed less than what the cost of treatment
is worth, will send myself and many of my colleagues into bankruptcy”. Similar
statements were also mentioned by 12 other respondents. Another respondent stated that
in order to improve access, more physicians have to increase the limits on their insurance
coverage, as this will increase the malpractice lawsuits, thereby increasing costs in the
long run.
Policies implemented to reduce health care costs, and or improve access to care
are viewed as health care reform to many of the participants. As Participant P10 stated,
“all policies will lead to a change in physician behavior. For example, the PPACA has
great intentions. However, moving from a fee-for service system, will directly and
indirectly lead to restrictions in access to health care provider. This will only lead to an
upheaval in the way many physicians practice”.
The theme PCP have little influence in affecting health care policy was identified
by 8 of the participants. Participant P2 stated that “Primary care physicians are really the
core of healthcare delivery. However, we have little ability to affect changes to the system
or its overall direction. Sometimes I feel powerless, but yet I still have to operate.
Sometimes I think we are powerless. I have been a primary care physician for almost 30

120
years, and I have never been more discouraged in our ability and willingness to participate
in the development or evaluation of health policies”. Similar statements were echoed by
three other respondents. Some shared the view that the younger aged physicians need to
become more involved in policy development and continued evaluation to save the primary
care health delivery system.
The theme of lack of interest in increasing the supply of PCP emerged through the
analysis of the question on how to correct PCP perceptions on the restrictions they face. As
stated by Participant P11, “sometimes it is difficult to know if it is the legislation that
restricts the supply of PCP. Before I became a doctor, there was a shortage of primary care
providers. Over the years, this has continued to decline while more new physicians are
more interested in specialized care. Those providers also have the same legislation, but
more people find specialized care more attractive”. Participant P6 also added that” it is
important for policymakers to know that PCP are in short supply and greater demand
whether as a result of legislation, market forces, or any other reason will directly or
indirectly impact the current supply of PCP”. Another respondent stated that “everyone
knows that there are not enough PCP. However, no effort has been successful in improving
the number of primary care physicians”. Interestingly, all PCP who work less than 40 hours
each week mentioned this point. None of participants who worked between forty and 60
hours per week mentioned this theme.
One of the themes identified by 13 of the 15 participants was the decreasing
remuneration PCP receive. Participant P6 stated that “the incomes of PCP have always
been lower than those of specialty care providers”. 8 participants mentioned the declining

121
income they have seen over the past 5 years. Participant P12 stated “this has little to do
with federal or state policies in my opinion. Even reimbursement from private health
insurers have been declining. As we speak, I am looking at some of the charges that I
have seen declined. I can no longer be reimbursed for many of the procedures I perform,
and when I am reimbursed, they are at a lower rate compared to those I received years
ago”.
Research question number 2, “what are the perceptions of primary care providers’
regarding reducing disparities in access” was answered by all 15 interviewees as well as
survey questions eight and 13. Table 12 shows the frequency of the responses for survey
question 8. Table 13 shows the frequency of the responses for survey question 13.

122
Table 12
Responses for Survey Question 8
Frequency
No
Impact
Great
Impact Total
Ongoing Medicare fee
changes 24 190 165 263 219 861
Implementation of
Electronic Medical
Records.
260 253 176 172 0 861
State and federal insurance
mandates. 221 266 109 126 139 861
Federal government
intervention. 43 15 229 385 189 861
Centers for Medicare and
Medicaid Services
sustainable growth rate
estimates and calculations.
259 274 328 0 0 861
Charity care requirements. 488 173 168 14 18 861
Medicaid’s high member-
to-PCP ratio 335 172 19 168 167 861
Note. Survey question 8, Please Indicate the Impact each of the following has on your
Practice

123
Table 13
Responses for Survey Question 13
Frequency
Not
Likely
Extremely
Likely Total
Medicare voucher system 22 119 270 270 180 861
More government regulation 378 292 179 2 10 861
Less government regulation 8 0 159 378 316 861
Increasing the number of
primary care physicians
educational facilities
23 4 22 538 274 861
Increasing the remuneration
of primary care physicians 17 5 0 150 689 861
Revising the
reimbursements
requirements without
significantly decreasing
PCP reimbursement rates
33 0 84 280 464 861
Expanded knowledge base
and resources for internal
improvement
11 30 1 339 480 861
Developing a health care
system that places greater
emphasis and value and
benefits of primary care
services
0 0 113 358 390 861
More effective and flexible
charity care mandates 44 0 234 402 181 861
Note. Survey question 13, Please rate how likely the following would remove the
restrictions on PCP practices and reduce disparities in access.
Desc
r
i
p
t
ive
Analysis
The six themes that emerged from this analysis were: pessimism in the future of
the US health care system, PCP will continue to work less hours each week, increasing
emphasis on chronic care will attract less PCP, improving health care access and quality

124
will remain a challenge for policymakers, mistrust of insurance companies, and health
care access can only be improved if PCP are directly involved in policy development and
evaluation.
Table 14 provides an overview of these themes which are supported by direct
quotes in the thematic analysis overview. The table displays the number of responses
from the semistructured interview participants. The following themes were identified in all
PCP based on the hours each participant stated that they worked each week. The table
displays the number of coded responses supporting each theme. Again, there were a total
of 15 participants in the interviews; four PCP worked less than 20 hours each week, three
PCP worked over 20 hours but less than 30 hours each week, three PCP work between 30
and 40 hours each week, three PCP worked between 40 and 60 hours each week, and two
PCP work more than 60 hours each week.

125
Table 14
Interview Responses and Themes of the Relationship Between Health Legislation and
Primary Care Provider Availability (N = 15)
Themes
<20
21
–
30
30
–
40
40
–
60
>
60
Theme
Total
Pessimism in the future of the US
health care system
2 3 2 1 2 8
PCP will continue to work fewer
hours each week 4 2 3 2 2 9
Increasing emphasis on chronic
care will attract less PCP
4 2 2 1 0 5
Improving health care access and
quality will remain a challenge for
policymakers
4 3 2 2 2 9
Mistrust of insurance companies
2 2 2 1 2 7
Health care access can only be
improved if PCP are directly
involved in policy development
and evaluation
4 3 2 3 2 10
Thematic Analysis
The theme of pessimism in the future of the health care system in the United
States emerged through analysis of the questions, what are your thoughts on the Healthy
Program Initiative to reduce disparities in access to health care services; and what advice
would you provide to health care stakeholders currently focused on reducing disparities

126
in access? Participants in all five groups expressed pessimism in the future of the US
health care system. Participant P1 stated that “over the past 10 years, this is the least
optimistic I have been in the future of health care delivery in the US”. Participant P4
stated “while I am in favor of the PPACA, it does no not do enough to attract more PCP.
Maybe other health care providers will be trained to be PCP, but with an increasing
population, it will be difficult to deliver adequate care with the current PCP workforce”.
Four of the respondents stated that the Healthy People Initiative has great goals.
However, “expanding the supply of PCP has been a goal for many years and in my
opinion will be a goal for at least the next century” said Participant P3.
“While not a perfect system, our quality of care ranks very high compared to
other developed countries” was the statement made by one respondent. Participant P5
further stated that, “more than eight of ten patients that I see have insurance coverage.
Yet many people with insurance do not get adequate care. By adequate I mean do not get
regular checkups, or utilize health services appropriately. Maybe legislation has
something to do with this, but I think it has more to with patients not utilizing health care
services until it’s too late”. Participant P6 echoed similar comments and added that “it is
no secret that PCP are few in numbers. However, until greater emphasis is placed on the
value and importance of primary care services, then the US will be filled with sick
persons”. Only one PCP working between 40 and 60 hours each week identified this
theme.
Participant P8 who works between 40 and 60 hours each week stated that “the
medical profession is in a decline. I spend most of my time on non-clinical duties and

127
spend fewer and fewer hours each week with my patients. I am sometimes frustrated
when I spend less time seeing my patients”. Participant P8 who works over 60 hours each
week mentioned in his comments that “I work for a living and I cannot afford to continue
seeing declining income in my practice”.
The theme PCP will continue to work fewer hours each week was one of the
themes that emerged from 13 participants. All 13 participants stated that they work fewer
hours last year compared to previous years. Participant P1 stated that “working fewer
hours translates to seeing fewer patients”. Five of these respondents stated that they plan
to cut back on hours worked and have even considered leaving primary care practice.
Participant P15 stated “if we continue to see decreasing reimbursement rates by private
and government insurers, we will not have any other choice but to leave primary care and
become educators, or serve in other capacities”. The profession has become less
financially rewarding and sometimes it is the least encouraging thing to see patients not
value their health as they should”. One of the participants in the group, “PCP working
greater than 60 hours per week”, stated that “I will continue to be a PCP for as long as I
am able to. It is what I was born to do. So until I can no longer do it, I will continue to
encourage patients to utilize primary care services”.
The theme increasing emphasis on chronic care will attract less PCP emerged
from the responses of 9 participants. Participant P10 stated “health care costs are high
because of chronic diseases”. Participant P1 stated that “patients are becoming sicker and
sicker each year. Health promotion is not important. Instead, it is all about treating
illnesses. Often times through discussions with my patients, I realize that more only

128
believe in seeing the doctor when they are ill. If we are here, and patients are not utilizing
our services, then this is the reason chronic illnesses are on the increase”. The other 7
PCP mentioned the need to promote preventing illnesses to reduce the increases in
chronic illnesses. None of the two PCP who work more than sixty hours each week spoke
about the increasing emphasis on chronic care.
Thirteen participants mentioned the challenges policy makers will continue to
face in developing more effective health policies. The theme improving health care
access and quality remaining a challenge for policy makers was mentioned multiple
times. Participant P8 mentioned that “many policymakers are not PCP and I believe that
this is one of the biggest problems with the policy making process. Policymakers need to
spend more time with PCP before making decisions. I think this is a major mistake. They
want to improve access, but have no idea what causes patients to not see PCP”.
Participant P13 stated “policymakers get paid to make best judgments. Unfortunately
these best judgments are anything but”. This Participant P6 further added that
“sometimes I wish they would be realistic and make policies that can actually work”.
The theme mistrust of insurance companies emerged from the responses on
reimbursement and payments rates. Both participants A and H mentioned the increasing
profits insurers make compared to the decreasing income of PCP. Participant P14 shared
an experience with an insurer’s decreasing reimbursement payments, as well as the time
it takes to receive reimbursements. As a result, this participant will not see patients who
have this type of insurance. Participant P11 stated “unfortunately patients are unable to
pay directly for much of the health services they are provided. So we must rely on third-

129
party insurers. While they are necessary to the medical profession, this compromises the
level of care patients received. Many of us have learnt the hard way that insurers are
often our worst enemies. We prescribe a treatment for our patients, and when they go to
the pharmacy, they receive other treatment options”. No participant differentiated
between government and private insurers in their responses.
All but one participant stated that health care access will only be improved if PCP
become directly involved in the policy development and evaluation process. Participant
P12 indicated that as long as things continue the way they have been for the past twenty
years, primary care delivery within the US health care system will continue to decline.
One of the statements on reducing disparity made by Participant P12 was “we have a
broken system filled with many band-aids. If things continue the way they are today, we
may not have many new PCP entering the field. Once I retire, I plan to become more
involved in the policy making process. I am not sure how far I will be able to go but with
my experience as a PCP, I will try my best to indirectly improve the lives of consumers
and the satisfaction of PCP”. Responses also included “there are policies that look good
in theory, but are detrimental to many PCP practices”, “sometimes policymakers really
do not know what works”, and “policymakers are failing health care providers and health
care consumers”. Additionally, PCP stated that after years of medical training it is
discouraging to face many of these challenges that can have been prevented.
Triangulated
Data
A
n
a
lysis
Triangulated data analysis is used to provide a more comprehensive account of a
phenomena being observed or studied using two or more research methods. Methodical

130
triangulation as explained by Thurmond (2001) is using more than one research method
to understand the studied phenomenon very well. One of the benefits of methodical
triangulation is “increasing confidence in research data, creating innovative ways of
understanding a phenomenon, revealing unique findings, challenging or integrating
theories, and providing a clearer understanding of the problem” (Thurmond, 2001, p.
254). The mixed method research design was selected to provide a picture of the
perceptions of the impact of health legislation on the practices of primary care
providers. According to Patton (1990), this dual approach will not present a clear-cut
picture, but can improve comprehension of the reasons for any inconsistencies between
the qualitative and quantitative data sets. These qualitative and quantitative data analysis
results for this study were also placed into previously identified categories mentioned in
Chapter 3 of interest in influencing health policy, importance of PCP involvement in
policy development and evaluation, satisfaction of the impact of health legislation on
PCP practices, and restrictions legislation has on providers’ practices. These categories
are being used to identify the overall perception of the impact health legislation on the
practices and scope of services offered by primary care providers.
Methodological triangulation was done to illustrate the predominant themes
between the qualitative and quantitative data collected. The coding and triangulation of
these qualitative and quantitative data in this study was done as a means to paint a
picture of the perceptions primary care providers share on any impact health access
legislation has on the delivery of services, as well as their views on improving access
and reducing disparities.

131
The coding of these qualitative and quantitative data also show how the
results
from
each of these analyses overlap with each other and support the findings of both sets
of data. Through the combination of qualitative and quantitative data in this section, an
over-arching view of knowledge, beliefs and perceptions in each of the categories is
provided. Table 15 provides a brief synopsis of the findings already discussed for each
theme.

132
Table 15
Triangulated Themes
Triangulated Theme Qualitative Quantitative
Interest in influencing health policy
PCP focus more on
daily requirements
rather than on
understanding health
policy
There is not a significant
relationship in the perception of
PCP survey respondents that are
interested in influencing health
policies.
Importance of PCP involvement in health
policy development and evaluation
Health care access
can only be improved
if PCP are directly
involved in policy
development and
evaluation.
There is a significant
relationship in the perception of
PCP survey respondents that
believe that PCP should be
involved in policy development
and evaluation.
Satisfaction of the impact of health legislation
on PCP practice
Pessimism in the
future of the US
health care system
There was a positive correlation
between satisfaction and the
number of hours worked each
week.
84.6 percent of PCP respondents
were either very dissatisfied or
dissatisfied with the impact of
health legislation on their
practices
Restrictions legislation has on PCP practice
PCP will continue to
work less hours each
week
71 percent of survey
respondents identified
uncertainty/changes in health
care reform, non-clinical
requirements, and
Medicare/Medicaid regulations
as the major restrictions

133
These categories are being used to identify the overall perceptions of primary care
providers.
Evidence of Quality
As stated in Chapter 3, this mixed methods research study used a sequential
explanatory design. This design follows a pattern of collecting and analyzing quantitative
data first, followed by collecting and analyzing qualitative data (Tashakkori & Teddlie,
2003).To support the quantitative and qualitative steps in this mixed method approach,
drafts of the survey and interview questions were forwarded to a group of eight health
care experts with extensive experience with health legislation and policy review. The
experts were asked to confirm, make additions, and recommend deletions. The experts’
recommendations were considered in a revision of the final survey and interview
questions.
The participants in the interviews were also involved in improving the quality of
the data. Within a week of the interviews with primary care providers, transcripts of their
interviews were sent to the interviewees for any necessary clarifications and approval.
There were only 2 additions. One PCP suggested that I added that the pessimism in the
future of the health care system only relates to physician reimbursement rates and
improved access. Another PCP stated that the mistrust of insurance companies relates
only to how they reimburse primary care providers. No PCP made suggestions with
regard to my interpretations of the data; however, they urged that the results be made
available to other health care policymakers.
In this study, interpretation of the data obtained from the survey responses were
used to as probing questions in the interview process. The semistructured interviews used

134
constant comparative analysis and the use of numbers to give weight to the interview
responses. Leech and Onwuegbuzie (2007) cited one of the most frequently used approach
in interpreting qualitative data is the use of constant comparative analysis. The use of
constant comparative analysis supports identification of underlying themes; using the
identification of chunks of information and the subsequent assignment of worded codes to
each chunk. Maxwell (2005) stated that many qualitative researchers give weight to
themes by using the words, for example, some, usually, and most, and that the use of
numbers to assign weights to themes can be valuable and legitimate.
Another example of credibility in my study is the result of the triangulation of
data. The data collected from participants used two different data-collection instruments.
In addition to the above measures, responses to the interview questions were compared to
similar responses on the survey to test for quality of the data and the results. Care was
taken to adequately describe the methodology of this research so that future replication
would be possible.
Summary
The purpose this study was to examine the role major health policies play in
restricting the availability of primary care providers. Chapter 4 described the data
collected during the study. Standard procedures of a sequential explanatory mixed
method design were used to conduct the analysis of this study. Research question one
consisted of quantitative and qualitative procedures and was addressed in that order. The
methods used for quantitative analysis were descriptive statistics, one-way ANOVA, and

135
Pearson’s chi-square correlation tests, using SPSS to determine relationships within the
items of the instrument.
In conducting this study, themes were identified from the analysis of the
perceptions of PCP of the impact legislation has on their practices and to assess their
views on reducing disparities in access. Analysis of the survey data revealed there was a
significant relationship in the knowledge in evaluating health policies among PCP who
work fewer than 20 hours, between 20 and 30 hours, 30 and 40 hours, 40 – 60 hours, and greater than
60 hours each week. The results of the analysis also found that even though there was a
significant relationship in the satisfaction of the impact of health legislation on PCP
practices among PCP who work fewer than 20 hours, between 21 and 30 hours, 30 and 40 hours,
40 – 60 hours, and greater than 60 hours each week, there was not normality in the data. The results
of the quantitative analysis found that there was also a significant relationship in the PCP involvement
in the past two years among PCP who work fewer than 20 hours, between 20 and 30 hours, 30 and
40 hours, 40 – 60 hours, and greater than 60 hours each week.
The qualitative analysis for research question 1 (RQ1) revealed that there were
several themes that emerged that included PCP focus more on daily requirements;
controlling costs, quality, or access affect physicians; PCP have little influence in
affecting policy; lack of interest in increasing PCP supply; and decreasing PCP
remuneration. Several themes also emerged from the qualitative analysis for research
question 2 (RQ2). These were pessimism in the future of the US health care system,
fewer hours being worked by PCP, increasing emphasis on chronic care will attract less
PCP, improving access and quality will remain a challenge for policymakers, mistrust of

136
insurance companies, and health care access can only be improved with more PCP
becoming involved in policy development and evaluation.
The triangulated data analysis revealed how the findings fit into specific categories
related to interest in influencing health policy, importance of PCP involvement in health
policy development and evaluation, satisfaction of the impact of health legislation on
PCP practice, and restrictions legislation has on PCP practices. There were similarities in
these qualitative and quantitative data in the areas of all four categories. This analysis
provided overarching themes for comparison of these qualitative and quantitative data.
Chapter 5 will offer an interpretation of the analysis of these data and a summary of the
findings of the study. The summary will include a discussion of how the data was
triangulated to corroborate quantitative data with the qualitative data. Chapter 5 will
begin with an introduction followed by interpretation of findings, implications for social
change, recommendations for action, recommendations for further study, and an overall
summary of the study.

137
Chapter 5: Discussion, Conclusions, and Recommendations
Introduction
The purpose of this sequential mixed-methods study was to examine the role
that major health policies play in restricting the availability of primary care providers
(PCPs) in the United States. Data were collected from 1,050 surveys were mailed and
869 surveys were returned. Eight of these were not included as pages were either
incomplete or respondents indicated that they have not been actively practicing. Fifteen
participants were interviewed from the twenty-five participants who returned a signed
consent form Interviewees were labelled P1 through P15. The data results from these
quantitative and qualitative phases were then used in a triangulated data analysis to
examine four areas related to PCP interest in health policy, importance of involvement in
health policy development and evaluation, satisfaction with the impact of legislation, and
the restrictions identified as a result of legislation. The triangulated data analysis
provided an overarching view of combined qualitative and quantitative themes.
This chapter presents the findings of this research study and answers to the primary
research questions and compares the data collected to the literature search findings in
Chapter 2. Chapter 5 also includes the recommendations for actions recommendations for
further research, implications for social change, and a chapter summary.
Interpretation of Findings
Interpretation of the findings will be done by each research question.
Research Question 1 (RQ1): What is the relationship between major health access
legislation and the availability of primary care providers?

138
H0: There is no relationship between health access legislation and the availability
of primary care providers to deliver services.
H1: There is a relationship between health access legislation and the availability of
primary care providers to deliver services.
Eight survey responses received were not included in the analysis due to
incomplete responses, and respondents indicating that they have not practiced within the
past five years. To answer research question one (RQ1), I entered the data from 861
survey responses into SPSS. The primary purpose for collecting quantitative data was
twofold; to analyze whether there is a relationship between health access legislation and
the availability of primary care providers, as well as to triangulate the survey responses
with the data collected later in interviews. Based on the findings in Table 15 and other
quantitative analysis in Chapter 4, there were significant relationships between
participants understanding health legislation, satisfaction with the impact of health
legislation on their practices, and their perceptions of including PCP in policy
development; and the hours worked each week.
Previous research has shown that there is a shortage of primary care physicians
and other primary care providers (Collins & O'Brien, 2011). The Patient Protection
and Affordable Care Act (PPACA), Healthy People 2020 Initiative, and other national
programs seek to increase the supply of primary care providers. According to Hagland
(2014), the PPACA will not increase the number of practicing primary care providers.
In an attempt to address the current shortage, in late 2014, the Primary Care Physician
Reentry Act was introduced in Congress. Though this act was never passed in

139
Congress, it sought to improve the nation’s primary care physician shortage by
providing training and financial assistance to doctors returning to medical practice in
exchange for their service as a public health provider (Hagland, 2014).
Physicians’ attitudes and behaviors related to their satisfaction have often
ignored the role the impact of legislation has on their satisfaction as well as how it
contributes to restricting their services. This study sought to explore the role
legislation has on PCP dissatisfaction and availability. Themes identified in this study
were knowledge and interest in influencing health policy, participation in health
policy development and evaluation, satisfaction with the impact legislation has on
PCP practices, and restrictions faced in delivering health services. Interpretations of
the findings have been provided according to each of these themes.
Knowledge and Interest
The description of knowledge and interest used for this study was the importance,
awareness, or attention health care providers place in the specific decisions and events
undertaken by policymakers to achieve a desired health outcome (Cherry & Trotter Betts,
2005). Survey questions number 4 and 5 sought to examine participants’ knowledge and
interest in the policy development and evaluation process. The analysis indicated that there
was a statistically significant relationship in participants’ knowledge in evaluating policy;
however, there was not a statistically significant relationship in participants’ interest in
influencing health policies.
An explanation for these findings was provided using step 1 of Patton and
Sawicki’s policy analysis model: identifying the problem. One concern Participants

140
P3, P4, P5, P6, P7, P9, P10, P11, P12, P13 all mentioned was a view that most
primary care providers do not understand related legislation, and instead focus on
their daily activities rather than on understanding health policy. Additionally, the
frequency data for survey question two showed that only 226 participants were either
interested or very interested in influencing policy development. As stated in Chapter
2, the role existing health policies have on the daily practices and the supply of health
care providers remain underassessed and misunderstood (Runy, 2009).
As Buchan (2010) stated, the lack of the stability and consistency in the practices
of health care providers contributes to a broken health care system. Buchan further
suggested that any attempts at real reform should begin with an examination of health
care policies enacted within the past three centuries and their effect on health care
provider practice in the United States. Feldstein et. al. (2013) stated that the PPACA is
confusing and this could be contributing to the lack of PCPs comprehension and interest
in health policy development and evaluation. PCPs can provide important perspectives
that could help optimize policy evaluation to improve future health outcomes (Feldstein,
et al., 2013).
One of the conclusions made in the Physician Foundation’s 2012 survey report
was PCPs have trouble fully understanding what policymakers are trying to achieve
(Physician Foundation, 2012). This finding was validated by the results of my own interview
analysis. A recurring theme that emerged from the interview analysis was that PCP focused
more on daily requirements or responsibilities rather than on understanding policies.
Participants P1, P2, P3, P4, P5, P7, P8, P10, and P13 all commented on the lack of PCP

141
interest in affecting policies. This finding was consistent with previous studies on PCP
involvement in policy development (Mittman & Sullivan, 2011). According to Buchan
(2010), the US health care delivery system is complex, but has at its core the relationship
between health care provider and patient. Enhancing PCP satisfaction and interest in
developing policies should be an important goal not only to attract more PCPs, but also to
improve the health care delivery system.
Participation
PCPs participating in policy development is a critical consideration in any health
care policy development strategies (MacDonald, 1992). The ANOVA results presented in
Table 9 that were conducted on the survey questions linked to participating in policy
development and evaluation, resulted in a p value less than the 0.05 significance level.
Similarly, recurring themes of the interview analysis suggested that PCPs believed that
health care access can only be improved when PCPs are directly involved in policy
developments.
Step 2 of Patton and Sawicki’s policy analysis model focuses on determining
policy objectives. The objectives listed in the PPACA and the Healthy People 2020
Initiative include a focus on increasing the number of primary care providers. According
to Pardes (2009), few proposals have led to the development of legislation that will
effectively address any possible restrictions health care providers face as a result of new
health care policy requirements. As discussed in Chapter 2, Abood (2007) cited the
increased participation of health care providers in policy analysis and development.
Despite this, the findings presented in Chapter 4 indicate a high percentage of PCP with

142
inadequate information and training on the PPACA. The theme of uncertainties in health
reform also supports the findings of Jacobson and Jazowski (2011) discussed in Chapter
2. If providers are not fully accepting of this new legislation, then these providers can
quickly become marginalized in the legislative process (Jacobson & Jazowski, 2011).
Respondents however, agreed that there are several benefits to policy development and
evaluation. Clearly highlighting the objective of each policy clearly may have an
increased effect on PCP participation.
The third step of Patton and Sawicki’s policy analysis model is establishing an
evaluation criteria. Providers stated that they spend less time on understanding the policy
development and evaluation process. Another theme emerging from the qualitative data
analysis is the uncertainties in health reform. As Jacobson and Jazowski (2011) detailed,
if PCPs’ fear of the uncertainties continue to grow, more has to be done to evaluate the
policy development. LeClair (2011) stated that the criterion must be precise and clearly
communicated between parties, including PCP delivering care. The interpretation of these
findings suggests that PCP participation and involvement in the policy development and
evaluation process can be more beneficial.
Satisfaction
Satisfaction was described as the extent to which a person's hopes, desires, and
expectations about the employment he or she is engaged in are fulfilled (Fortney,
Luchterhand, Zakletskaia, Zgierska, & Rakel, 2013). Four survey questions assessed PCP
satisfaction: 3, 9, 18, and 20. The ANOVA results showed p values < 0 .05 significant
levels. Fortney et al. (2013) stated that the low work satisfaction of primary care

143
physicians is a growing concern and this can have a negative influence on health care
policy development. Derose, Gresenz, and Ringel (2011), stated that in order to reduce
disparities in health care, it is important to first understand the inequities that contribute
to the dissatisfaction of health care professionals.
Step 4 of the policy analysis model focuses on identifying alternatives. Thirty
percent of the number of respondents stated that low reimbursement rates
contributed to their dissatisfaction as a PCP. Other notable factors included non-
clinical duties, fee-for-service requirements, and decreasing autonomy. Survey
question 13 sought to examine how likely several factors may remove restrictions on
PCP practices. Six hundred and eighty nine respondents identified increasing
remuneration rates as extremely likely to remove restrictions. Revisions to the
remuneration levels PCP receive, as well as expansion to the knowledge base for
internal improvements were the other likely factors PCP identify that can remove
these restrictions.
As a means of triangulating the data, the interview analysis was used to
validate this finding. During dialogue with interview participants, 8 participants
mentioned their pessimism in the future of the US health care system. Nine
participants believed that PCP will continue to work fewer hours each week. As the
quantitative data analysis shows there is a positive correlation between satisfaction
and the number of hours worked each week, focus should be placed on developing
alternatives aimed at improving PCP satisfaction. This finding is congruent with
previously conducted studies that have reported positive correlations between the

144
satisfaction of primary care providers, patient satisfaction, and improved care
(Jacobson & Jazowski, 2011).
Restrictions
Jacobson and Jazowski (2011) discussed restrictions as the resulting
consequences of the inability to ensure access to quality, and culturally competent care.
Data analysis related to restrictions resulted in no significant results from the quantitative
statistical test results. No items from the one way ANOVA (Table 9) produce results that
indicated that restrictions affected the number of patients seen daily. However, Table 7
show that non-clinical duties, uncertainties in health reform, and Medicare / Medicaid /
Government regulations were reported as the leading issues that restricted the scope of
services offered.
The themes that emerged from the qualitative data analysis relating to restrictions
were pessimism in the future of the US health care system, and the continued decrease in
PCP working hours each week. These themes were also consistent with the findings of
the Survey of America’s Physicians conducted in 2012 and the concerns of the future of
America’s primary health care which discussed how providers are frustrated to the point
of openly criticizing payers (Hagland, 2014).
R
ese
a
r
c
h
Question 2 (RQ2): What are primary care providers’ perceptions regarding
reducing disparities in access?
Survey question 13 asked respondents to rate how likely nine factors may be able
to remove restrictions PCP face in their practices and reduce disparities in access. Using a
Likert Scale of 1 – 5 (Not Likely to Extremely Likely), a total of 839 respondents

145
selected numbers 4 and 5 as their response to increased remuneration of primary care
providers. Using the same Likert Scale, 819 respondents selected the option “expanded
knowledge base and resources for internal improvements” as more likely or extremely
likely to reducing health disparities. Zero respondents selected options 1 or 2 on the same
Likert scale for option “ Developing a health care system that places greater emphasis
and value and benefits of primary care services” for this question.
During the interview PCP were asked to describe their perceptions on improving
access and reducing disparities. Nine participants (P1, P2, P3, P4, P6, P9, P10, P12, and
P14) believed that health care access will continue to be a major challenge for health care
policy makers. The theme health care access can only be improved if PCP are directly
more involved in policy development and evaluation, were identified in the data collected
from ten of the interview participants.
Steps five and six of Patton and Sawicki’s policy analysis model are focused on
assessing the possible alternatives, and implementing and evaluating new policies. These
alternatives must be comprehensive and their advantages and disadvantages explored. In
the Health People 2010 Final Review – Complete Report published in 2013, Object 01-
05, persons with a usual primary care provider did not meet its target of 85 percent
(Centers for Disease Control and Prevention, 2013). In fact, between the assessed period
1998 – 2008, the rate met was between 76 and 78 percent (Centers for Disease Control
and Prevention, 2013). In creating the Healthy People 2020 Initiative, new objectives
were added including ones related to the primary care workforce (Centers for Disease
Control and Prevention, 2013).

146
While this study did not assess all legislation, or explore in depth alternative
procedures to the policy evaluation process, both the quantitative and qualitative data
analysis demonstrated the need to begin assessing current or alternative solutions to
reducing disparities. Participant P9 mentioned that primary care providers are ignored or
silenced in health care policy decision making. Participant P9 commented further that
PCP are not able to advocate for themselves or the profession. In examining the
responses to survey questions eight and thirteen, policy makers are able to review the
issues that may have “no impact” or “great impact” on reducing the restrictions PCP face,
as well as those issues that are “not likely” or “extremely likely” to reduce disparities and
improve access to primary care services.
One of the topics discussed by all interview participants is health reform. Some
respondents discussed creating greater emphasis on primary care, increasing the supply of
primary care physicians, reassessing remuneration processes, as well as increased PCP
participation in policy development. Many agree that these will be in some type of
reform, however, there are differences in perspectives in how to achieve these results.
One respondent suggested having less government intervention in physician
remuneration discussion, while another suggested less could lead to further inequities in
physician income levels. The findings of this study display why primary care providers
are not available to provide care based on their perceptions of existing health legislation.
Limitations of the Study
There were several limitations to this study. Primary care providers in this
study are physicians designated as those
practicing
family medicine, general internal

147
medicine, or pediatrics. Data was not distinguished by primary care specialty to
provide practice-specific analysis. Availability was measured as the number of
hours primary care providers spend each week seeing patient and were divided into
five groups. The sample size for each group was not evenly distributed. Future
research should make an effort to have data collected from groups with sample sizes
evenly distributed. Also the demographic data collected for these qualitative and
quantitative portions were collected from a mix of male and female participants and
groups were not evenly distributed. This did not allow for these data to be analyzed
deeper looking at the differences in this population. Data used for these qualitative and
quantitative portions of this study were only collected from primary care providers
who are currently practicing. This prevented these data from being generalized to other
types of health care providers. Additionally, qualitative data collected utilized only15
participants.
Recommendations for Action
In light of these findings I suggest four recommendations for action. The first
recommendation is for health care policymakers relating to increasing the number of
primary care providers. The Agency for Healthcare Research and Quality (2015)
estimates that in 2010, there were 208,208 practicing primary care physicians in the
United States 2015. According to the 2010 American Medical Association Physician
Masterfile approximately 30% of new physicians are entering primary care practice
(United States Department of Health and Human Services, 2013). Policymakers
should review how policies are preventing expanding the primary care workforce.

148
The findings of this study indicate that the primary care providers are pessimistic in
their views on the health care system. Many respondents mentioned the lack of
interest in increasing the supply of practicing primary care physicians. Policymakers
also need to re-examine the effectiveness of existing policy and increase the participation
of PCP in policy development and evaluations. For example, by expanding educational
and training programs, PCP can become more interested in policy development and
evaluation, or be more prepared to lessen some of the restrictions and dissatisfaction they
currently experience.
One of the Healthy People 2020 objectives is to increase the number of practicing
primary care providers (U.S. Department of Health & Human Services, 2013b). The
findings of this study can be incorporated into designing specific methods to meet this
objective. Respondents stated that primary care providers should be involved in health
care policy development and evaluation. While this study did not provide detailed
analysis by practice region or state, its findings can be used by not only the Healthy
People Initiative, but also by local partners in their efforts to attract new health care
providers to their communities. By understanding the availability of providers in each
community, local health stakeholders can not only develop community-specific policies,
but also will be able to attract more providers to their communities. How primary care
providers feel about policy development and evaluation has an impact on the
effectiveness of these objectives and other policies.
Both opponents and proponents of the PPACA agree that more effective
strategies or legislation are needed to improve access and utilization of health

149
services. While this legislation aims to expand access to health services, concerns
exist about how this will affect the health care workforce. With the focus on
preventive care, the current shortage in the number of primary care providers
suggests that the workforce may be inadequate to meet the current and future health
needs of the population. While it is true that this and other health policies have been
implemented to expand the health care workforce, disparities in access will remain
prevalent until the restrictions PCP identify that limit the availability of health care
providers are identified and addressed. Any attempt to address disparities in access
should examine the supply and availability of the health care workforce through
policy analysis and evaluation.
Policies must be continually assessed. To health care educators, I would
recommend revising medical school curricula as well as physician continued education
and training programs. Previous studies have shown that physician dissatisfaction may
have an adverse effect on health care outcomes, quality, and cost (Sommers, Swartz, &
Epstein, 2011). By improving health education programs, physician satisfaction may be
enhanced as providers’ tolerance for uncertainty in daily care may be enriched as their
knowledge of and increased participation in policy evaluation are expanded. The findings
in this study show that physicians do not understand many health policies, and are not
optimistic about the future of the health care delivery system. Participants agree that
primary care providers should become more involved in health policy development. One
finding show that providers learnt of the PPACA through magazines or other media
sources.

150
Recommendations for Future Research
This doctoral study focused on the knowledge and perceptions of primary care
providers evaluating the role of legislation on PCP availability and reducing health
disparities. Future studies on this topic should explore both knowledge and perceptions to
gain a deeper knowledge of not only primary care physicians, but other health care
providers. This study used a modified version of a survey instrument developed and
tested in 2012.
Future
research on this topic should enhance these quantitative instruments
to assess the impact of new legislation such as the PPACA on primary care providers’
availability. More qualitative studies should be conducted to continue improving health
care delivery.
Findings specific to the satisfaction of the impact of health legislation on
provider practices can be used to guide future research. The finding of approximately
85% of respondent responding that they were either dissatisfied or very dissatisfied with
the impact of health legislation on their practices should be further analyzed and
recommendations provided to health care policymakers.
More sequential mixed method studies utilizing qualitative data to probe deeper
on survey data would be useful to gain additional information surrounding improving
access to care in local communities. The study can be replicated using different research
questions such as (a) How does the PPACA affect the scope of services PCP provide?,
(b) Is there is significant difference between PCP satisfaction before the PPACA, and
after the PPACA?, (c) What are health care providers’ perceptions on improving the
remuneration rates and process? Another recommendation is to conduct a comparative

151
study of primary care providers’ perceptions with specialty care providers’ perceptions
of the effectiveness of provider input in health care policy development and evaluation.
Implications for
Social
C
h
a
n
ge
Positive social change is “a deliberate process of creating and applying ideas,
strategies, and actions to promote the worth, dignity, and development of individuals,
communities, organizations, institutions, cultures, and societies” (Walden University,
2013, p. 5). The PPACA has been implemented with much critique. One of the provisions
of this health legislation is the $230 million funding allocated to increasing the number of
primary care providers (United States Department of Health and Human Services, 2011).
Many health care stakeholders estimate that this will attract approximately two thousand
more primary care physicians by 2015. While expanding the PCP workforce is welcomed
by many respondents in this study, more needs to be done to expand primary care
physicians’ availability. In order to improve health care access and reduce disparities,
health care stakeholders must re-evaluate how existing policies impact health care
delivery. There are several implications for social changes in this study.
One implication is designing more effective policy evaluation and development
methods or processes. One of the findings identified in this study is the low satisfaction
on the impact of health policies on PCP practices. As shown in the findings in Chapter 4,
no respondent stated that they were satisfied or very satisfied with the impact of health
legislation on his or her practice. Subsequently, many state their lack of optimism in the
future of health care delivery. While fair and equitable policies should be implemented, it
is clear that the impact of these policies is either underevaluated or misunderstood by

152
policymakers. The findings in this study can be incorporated into enhanced policy
evaluation and development practices and procedures, which can increase the number of
new PCP entering active practice as well as the retaining physicians in the workforce.
The data findings indicate that not all primary care providers understand existing
legislation. Another implication for social change this study provides is the potential to
influence PCP education and training. Not only can programs be developed to improve
the knowledge of primary care providers of the intended impact of health polices, other
health care providers, administrators, and stakeholders can benefit from improved
training and evaluation opportunities.
One of the greatest implications for social change this study is its possible
contribution to reducing health disparities and improving access to health care providers.
As McLeod, Klabunde, Willis, and Stark (2013) stated, physician satisfaction and their
availability to provide care contributes to the quality of the health care delivery system.
Greater physician satisfaction is associated with more appropriate prescribing practices,
patient adherence, and greater patient satisfaction (McLeod, Klabunde, Willis, & Stark,
2013). Previous studies indicate that there is a relationship between physician satisfaction
and patient satisfaction (Feldstein, et al., 2013). As the findings show, the less satisfied
primary care providers are with the impact health legislation has on their practices, the
fewer hours they are available to provide patient care. This study will influence health
care policymakers to review current and future efforts to expand access to health care
providers. Less satisfied PCP results in higher turnover, as well as higher indirect costs
such as physician recruitment. This study can contribute to strategies aimed at improving

153
PCP satisfaction, which may lead to higher PCP retention rates, greater patient
satisfaction, lower facility costs, improved access, and improved health status of patients
who utilize these health care facilities.
This study can assist stakeholders in analyzing and evaluating existing health care
access policies. Through policy analysis and evaluation, health care stakeholders can
develop new legislation that will reduce the disparities in access to health services and
providers. Understanding the sources of primary care physician dissatisfaction can
improve not only health care access and quality but also reduce health care costs.
Identifying the relationship between major health legislation and the adequacy and
availability of health care providers to practice, can not only add to the scholarly
literature library, but also improve access to health services, reduce other types of
disparities, as well as improve the quality of services delivered.
Conclusion
Even as rates of uninsured patients begin to decline, primary care physicians’
availability to deliver care remains an important topic in health care access, quality, and
costs. This study’s findings revealed important factors for researchers, health educators,
health care policymakers, and other health care stakeholders. Access to health care
services involves much more than expanding health insurance coverage or increasing the
numbers of practicing physicians. While the other sources of physician dissatisfaction
were not assessed, the study’s finding indicate that many do not fully understand policies
including the PPACA and are dissatisfied with the impact health legislation has on their
practices. Since there is a positive correlation between physician satisfaction and the

154
number of hours they work each week, efforts designed to expand patients’ access to
health services must include addressing the sources of physician dissatisfaction.
Addressing sources of physician dissatisfaction may increase the number of
patients they see daily. If physicians fully understand legislation such as the PPACA they
may be prepared to address both the positive and negative impact of this legislation. This
knowledge can then be incorporated into health policy development and evaluation. Also,
increased knowledge and participation may be integral into reducing the pessimism
identified in the results presented in Chapter 4.
Efforts to increase the number of practicing primary care physicians are evident in
studies focused on the physician workforce (United States Department of Health and
Human Services, 2013). As the quantitative data analysis in this study indicate; there is a
significant difference in the perceptions of PCP of the importance of including PCP input
in developing health policies between PCP who work fewer than 20 hours each week.
There was also a significant difference in satisfaction of the impact of health
legislation on provider practice. There was a difference in the satisfaction of PCP who
work between 30 and 40 hours each week, compared to those who worked less than 20
hours each week. Themes that emerged from the analysis of qualitative data pertaining
to satisfaction showed that many will continue to work fewer hours each week, and the
pessimism in the future of America’s health care delivery system. Participants P1, P2,
P3 and P4 who work fewer than 20 hours each week stated that they believed that PCP
will continue to work fewer hours.

155
Declining PCP remuneration rates was a theme identified in the data obtained
from 13 of the 15 interview participants. Similarly, 13 participants stated that efforts to
control cost, quality, and access will continue to affect the supply of physicians. The
findings that arose from this research indicate that PCP input is important in the policy
development and evaluation processes, however, very few PCP fully understand
legislation including the PPACA. Future studies are recommended to assess the actual
impact this new legislation has on PCP practices, and recommendations provided to
policymakers. Many PCP supported having an expanded knowledge base of resources to
improve training and comprehension of legislation. This study’s findings can contribute
to not only developing more effective PCP satisfaction programs, but also strategies that
can improve access to health care services and reducing disparities.

