


1
Introduction
Humla district is a rural and poor region of Nepal, stranded in the Himalaya
mountains (Justice 1986, 5). It lacks infrastructure in many areas, specifically health care
(Adara 2014). NGOs are common in this region of Nepal, providing health care,
education, and sanitation technologies to the residents (Sanders and McKay 2013, 109).
One NGO conducted a qualitative improvement (QI) study in this region, using a Mobile
Medical Camp (MMC) to deliver health care. The study focused on gathering data to gain
information on how better it can improve its services. As part of my thesis, I used this de-
identified data to conduct analyses to identify socioeconomic barriers on health care
seeking behavior.
The Rural Region of Humla, Nepal
Nepal is among the poorest countries in the world (Citrin 2011, 16). The 2011
Human Development Index (HDI) indicates that as much as 40% of Nepal’s population is
below the poverty line. Nepal’s poverty rate was ranked 157th out of 187 countries in the
world in 2011 (Daniel 2012, 6-7).
Nepal is divided into three zones: the northern Himalayas (the mountains), the
central hills (the hills), and the flat southern plains (the Terai) (Daniel 2012, 7). The
district of Humla lies between 81 and 82 degrees longitude and 30 degrees N in latitude
(McKay 2002, 241) in the far northwestern corner of Nepal in the central Himalayas
(Justice 1986, 5). It is bordered by China, which was formerly Tibet (Grocke 2013, 1).
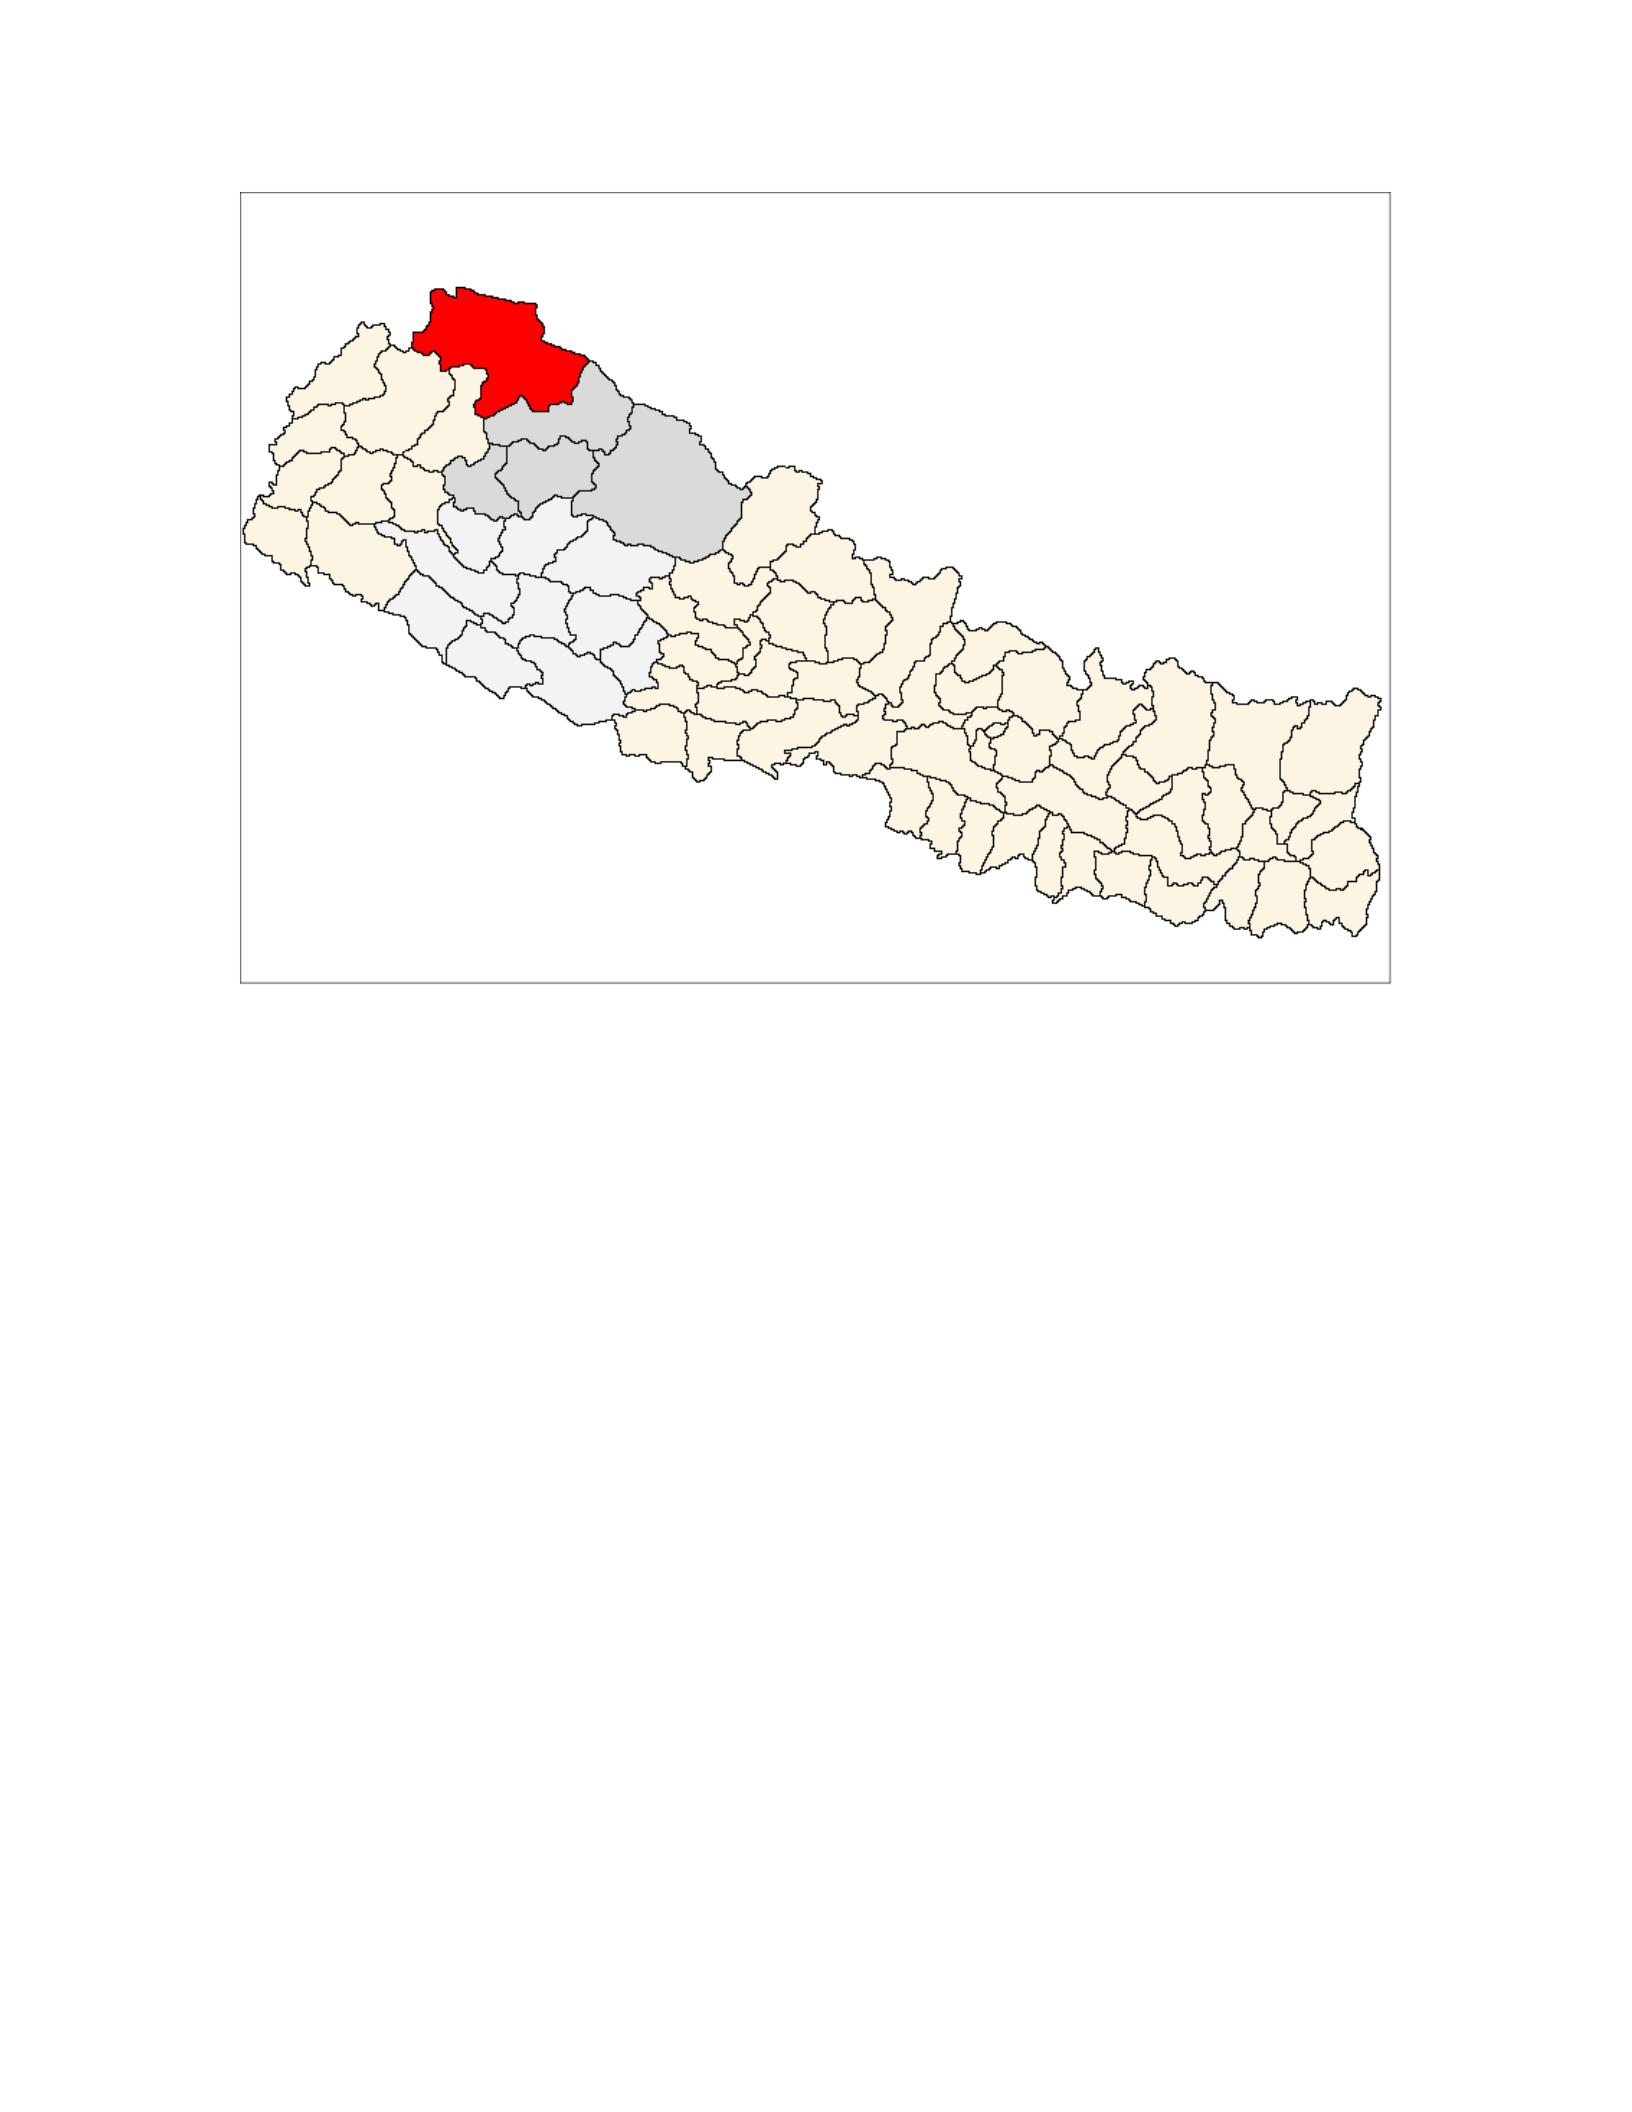
Figure 1 shows a map of Nepal. Humla district is shown in red.
2
Figure 1: A map of Nepal with Humla district in red (Wikipedia 2014)
Within Nepal, Humla district is at a disadvantage, being isolated from the rest of
the country in the high mountains (Adara 2014). “A peripheral area in a peripheral
country, Humla is a vast and road-less mountain region that consistently ranks at or near
the bottom of Nepal’s 75 districts on many socio-demographic and health parameters”
(Citrin 2011, 20). In 2011 it had the lowest literacy rate in the country; 47.8% compared
to a national average of 65.9% (Central Bureau of Statistics 2012, 4, 226-260).
Different crops are grown seasonally: rice, maize, and potatoes from April to
June, wheat from October to November, and apples from December to January. The
summer and growing seasons are short and affected by avalanches, floods, landslides,
fire, storms, droughts, glacial lake outbreaks, and rocky terrain. The region’s high
elevation (1,524 - 7,337 meters) and geographic conditions lead to a short growing

3
season and high food insecurity (UNFCO 2013, 2, 10-11). The winter is long and harsh
with temperatures ranging from 25 to -28 degrees Celsius (UNFCO 2013, 11).
There are no roads in the entire district or in connection “to the rest of the
country” yet, although the Hilsa-Simkot road is currently under construction. This road
will eventually connect Humla district to Tibet (UNFCO 2013, 1-2). Simikot, the district
headquarters, is only accessible by foot or airplane. Because planes are unreliable due to
weather conditions and unaffordable for most residents, most areas in Humla are only
accessible by foot and “can be reached only by walking for hours or even days along
steep, winding trails” (Justice 1986, 5).
The Maoist conflict, which is now largely over and lasted from 1996 to 2006
(Basnett 2009, 4), has had a large impact on the difficulty of travel in remote places like
Humla (cf. Citrin 2012, 74). The main Humla-Karnali River, as well as 50 other smaller
rivers, divide Humla district. The rivers “…are uncrossable when swollen by monsoon
rains and melting snows, [and] they are during much of the year” (Justice 1986, 5). There
used to be 27 suspension bridges connecting different parts of Humla together, however,
the Maoist conflict destroyed many bridges during the war. In 2013, many bridges were
still not functional (UNFCO 2013, 1-2).
Due to the geography and climate, the elevation, and the loss of bridges, most
villages are cut off from the outside world for up to four months out of the year (UNFCO
2013, 11). Development of infrastructure, including transportation, communication, and
health care, has been hindered due to the isolation of rural areas from big cities and
government. Geographic distance, as well as the mountainous terrain, provides difficult
barriers to overcome. This leads to the division and isolation of rural areas (Justice 1986,

4
5). Infrastructure is poor, education is limited, and paid employment is low due to the
prevalence of a non-cash economy (Adara 2014).
As with many other economically developing countries, Nepal endures health
challenges (Dupas 2011, 2). However, Humla seems to be at a greater disadvantage than
even the rest of Nepal. Preventable and infectious illnesses are amongst the highest in the
country. Over 60% of the district’s population suffers from stunted growth and 15% are
severely underweight. Fifty-three percent of children below five years of age suffer from
anemia (UNFCO 2013, 9). Food shortages are common; only 10% of the district has
enough food for an entire year (UNFCO 2013, 11).
The main health concerns are severe malnutrition, critical respiratory infections,
childbirth, and complications due to heavy worm loads and Hepatitis B, which is endemic
in this population. Respiratory diseases are common due to smoking and indoor air
pollution caused from fire-burning stoves. Lack of sanitation and hygiene technologies
lead to food and water-borne diseases. Steep mountain paths produce injuries from falls
and landslides. The local subsistence system is based on the practice of raising livestock,
agriculture and long distance pedestrian trade. The work is taxing and only exacerbates
the burden of disease (Sanders and McKay 2013, 110; UNFCO 2013, 8).
For most of these diseases and ailments there are appropriate treatments, yet still
these diseases continue to cause morbidity and mortality. Worldwide, 6-70% of child
deaths are due to deficiency in seeking health care (O’Donnell 2007, 2821). People in
economically undeveloped countries are strongly affected by infectious and parasitic
diseases that render receiving health care of great importance in order for children and

5
adults to lead as long and healthy lives as people in more economically developed
countries (Dupas 2011, 2).
Theoretical Concepts to Consider
“The ‘quest for therapy’ all over the world is an important research issue since it
reveals essential elements of people’s social behavior and provides insights into their
perceived needs for different kinds of health services” (Kroeger 1983, 147). This research
will draw upon the theoretical framework of critical medical anthropology and focus
specifically on the political economy of health. It will draw upon a conceptual model
within the greater social sciences: the health behavioral model. It will combine the
political, economic, social and cultural determinants of health care seeking behavior to
provide a rounded theoretical investigation.
Critical medical anthropology is founded upon the idea that “change programs
should not be attempted unless one also studies the social production of illness and
poverty within the larger dynamics of class interactions, colonialism, or world economic
systems” (McElroy 1996, 7). Marxist and dependency theory both influenced critical
medical anthropology in its analysis of “…the impact of global economic systems,
particularly capitalism, on local and national health” (McElroy 1996, 7). As Baer has
suggested, access to health care is influenced by cultural and historical conditions, as well
as hegemonic systems of power. The idea of accessible health care depends upon “how
and in what form… this power [is] delegated, and how this power is expressed”
(Alexandrakis 2001, 75). In order to study health care seeking behavior, it is crucial that
first the “political, economic, social and environmental conditions [are identified] within
a particular society or group” (Alexandrakis 2001, 76).

6
Across the field of social science, social psychology’s health behavior model is
one of the oldest and best known (Hausmann-Muela et al. 2003, 9). This model suggests
that health care behavior is a combination of 4 factors: perceived susceptibility, perceived
severity, perceived benefits and perceived barriers (Coreil 2008, 76-77). Hyder and
Morrow suggest that the strongest predictive factor on health care behavior is perceived
barriers (2005, 51). Focusing on perceived barriers as the strongest predictive factor on
health care behavior makes the health behavior model relevant in measuring the costs and
benefits of accessing health care services (Coreil 2008, 76-77).
Although the health behavior model is most often used within the realm of health
promotion, it can be applicable towards understanding individual health seeking behavior
patterns. According to Mackian, this model’s downfall lies in assuming the decision-
maker is a purely rational being (2003, 8). As Ward, Mertens, and Thomas has suggested,
it is not rational to assume “that recognition of symptoms will necessarily or
automatically result in health seeking behavior” (Bork-Huffer 2012, 25).
This thesis will use analyses to show patterns of association, however, it will not
underestimate an individuals’ capacity for agency and resistance (De Los Angeles Nunez
Carrasco 2008, 40). It is important, especially as an anthropologist, to remember, “health
and illness are defined, labeled, evaluated, and acted upon in the context of culture”
(Hyder, Morrow 2005, 41). The health behavior model also “neglects determinants… like
previous experiences, advantages of mal-adaptive behavior, behavioral intention,
perceived control etc.” (Hausmann-Muela et al. 2003, 10). Although this thesis will be
based upon quantitative data and analyses, qualitative search for meaning and reasoning
will be pursued to explain possible determinants.

7
Impacting Rural and Economically Undeveloped Regions Through this Research
The health infrastructure is weak in Nepal. Mobile medical camps (MMCs) are
common there, as well as other parts of the world. They function to provide health care
resources that are not available through the government system of sub health posts, health
posts and district and regional hospitals. Although MMCs are problematic for a variety of
reasons, they continue to play a role in health care delivery in remote settings the world
over.
In order for Humli residents to become healthier, NGOs working in the region
believe health care seeking behavior must evolve. In order for health care seeking
behavior to change, we need to better understand current health seeking behavior
patterns. This project is an analysis of one such attempt by an NGO to gather health and
social information about patients, in order to create a lasting and long-term health
partnership with this community and individuals within it.
MMCs and their outcomes are poorly understood. In order to broaden our
understanding of how an MMC might be perceived by a local person, an NGO working
in remote Humla decided to collect not just clinical data, but also social, economic, and
attitudinal data from patients. Because these data address health care seeking behavior,
this is primarily the literature that I have engaged with. This thesis is a study and analysis
of data collected by the NGO staff on patient socioeconomics and logistics of travel.
The first set of analyses presented here explores whether socioeconomic status
(SES) has an effect on health care seeking behavior. This section of the project addresses
the household level trends and barriers against seeking health care. Results show how key
socioeconomic factors affect health care decision making within a group of individuals

8
seeking health care from local government and private clinics as well as MMCs in the
Humla district of Nepal.
The second set of analyses presented in this thesis represents an attempt to better
understand the logistics of travel needed to obtain health care in a remote and
mountainous region, such as Humla. Although health care seeking behavior is heavily
“influenced by the distance [the patient has] to travel… few studies have tried to estimate
these distance effects” (Muller et al. 1998, 878). Jolly and King were the first to
quantitatively demonstrate the effect that travel distance has on the utilization of health
care services (Kroeger 1983, 151-2). This thesis will explore travel routes, distances, and
elevation gains and losses required for villagers to access health care. The primary intent
behind these analyses is to better understand the role of distance decay (the decrease in
utilization with distance) in local people’s health seeking behavior (Mueller et al. 1998,
878).
Results from these analyses may add towards a greater understanding of health
care seeking behavior. Ultimately, results from this thesis can be of aid to the major issue
“how can the benefits available to the few be expanded to meet the needs of the many?”
(Balabanova et al. 2006, 2). Results may help NGOs be able to provide more adequate
services in Northwestern Nepal. Specifically, results may propose better locations for
MMCs in Humla district. These revised locations will make health care more easily
travelable and accessible for patients.
Results may have broader implications for similar geographic regions. Findings
related to socioeconomic factors and travel logistics of seeking health care can be used
for geographic regions that have similar climates and health care resource limitations. An

9
important part of providing successful local health care is the study of how people use
health care facilities (Kroeger 1983, 147). The results of these analyses will be helpful to
villagers located in rural and high elevation areas and to the NGOs working within
similar regions all around the world. This thesis benefits the villagers within Humla
district, the broader community, and the larger anthropological community.
I have already discussed the geographic vulnerabilities of Humla, Nepal. Next, I
review literature based upon the barriers that prevent people from seeking health care. It
will focus specifically on socioeconomic barriers. Then I discuss the weak health
infrastructure in Humla. Finally, I will talk about Mobile Medical Camps (MMCs) and
address their pros and cons on the community.
After the literature review, in order to better understand the relationship that
socioeconomics has with health care seeking behavior, I will report results from data that
were collected from six MMCs in northern Humla in 2013. To show hardship of travel
and inaccessibility of health care access, I will show a map of 26 commonly used routes
in Humla district. I will conclude with a discussion of my results.
It is important to define health care seeking behavior, as this term can cause
confusion. It is “…conceptualized as a ‘sequence of remedial actions’ taken to rectify
‘perceived ill-health’ (Ahmed et al. 2000)” (Mackian 2003, 7). Health care seeking
behavior can include both formal and informal methods of seeking health care. This is
different from health seeking behavior, which is more heavily adopted in psychology and
looks at the general idea of what it means to be healthy (Mackian 2003, 7). Health
seeking behavior focuses on health-promoting behaviors as opposed to actions one takes

10
when one is sick. Due to the database I worked with, the focus of this thesis is health care
seeking behavior. This focus is most appropriate for the data being analyzed.
Review of Literature: Barriers that Prevent Accessible Health Care
Convincing amounts of literature demonstrate that the issue of health care
accessibility continues to be a prominent problem in economically developing countries
(O’Donnell 2007, 2821, 2830). However, accessible health care has come to have
different meanings for different people. There are many definitions that relate to the term
access to health care. Sometimes access to health care is only defined in its reference to
geography. Penchansky and Thomas refer to it as a combination of four individual parts:
affordability, availability, acceptability, and accessibility. While some people understand
it to mean “… the opportunity to use health care; others draw no distinction between
access and use” (O’Donnell 2007, 2821). O’Donnell “proposes that the central concern is
whether individuals that can potentially benefit from effective health care do in fact
receive it” (2007, 2821).
Barriers to health care are categorized as either supply-side or demand-side. Ensor
and Cooper believe that demand-side barriers are determinants of health care use that are
not dependent on price or service delivery. They would consider cultural and social
barriers, education, opportunity cost, and distance all to be considered demand-side
barriers (Ensor, Cooper 2004, iii). Barriers to accessible health care are often not clear
because they “…may interact and influence each other” (Jacobs et al. 2012, 290). A
barrier might act as both a supply and demand-side barrier in different ways. This thesis
will first address demand-side barriers that prevent people from accessing health care. It
will then look at MMCs as a potential solution to supply-side barriers.

11
A person’s resources, or lack thereof, can act as a barrier to accessing health care.
There are many forms of resources that a person might need in order to seek out health
care; these include material resources, human resources, and social resources. Each of
these factors has an effect on one’s ability to access health care in different ways.
Material resources can include physical, natural, and financial capital. Physical resources
include transportation. Natural resources include ownership of livestock or land, which
lends to being wealthier. Financial resources include cash or credit. Human resources
include one’s level of education and ability to obtain information. Social resources
include one’s social support network that can include family, friends, and neighbors who
are willing to make sacrifices to help a person whom is seeking health care (Bakeera et
al. 2009, 6-10). Due to the data available, this thesis will focus on material resources that
help to build a person’s SES; primarily including natural and financial capital.
It is hard to measure the reasons behind health care seeking behavior. It is much
easier to measure the quantifiable effects (e.g. who is accessing health care and what
health care is being offered). Oliver and Mossialos argue that scientists oftentimes put
more effort into researching the availability of health care instead of the utilization of
health care. The utilization of health care can be unquantifiable and messy. Tipping and
Segall understand utilization to be more easily measured and “…a frequent proxy for
access” (Balabanova et al. 2006, 2).
Information, reliability and reputability of the information provider, ability to
process information, education, and time to adapt to new information or new technologies
are all barriers that must be overcome in seeking health care (Dupas 2011, 9-15, 29).
Gender discrimination, socioeconomics, and geographical distance are also critical

12
factors in one’s ability to access health care (Deogaonkar 2004, 1). The weaknesses
involved in supplying health care include producing and providing inadequate quality of
health care and insufficient resources. The supply-side of health care also errors in
inappropriately allocating resources across levels of care, regions, and programs (Dupas
2011, 9-15, 29; O’Donnell 2007, 2826).
The dissemination of information can be achieved through numerous forms, such
as social networking (e.g. family, relatives, acquaintances, friends), media (e.g. TV,
radio, internet, newspaper), information campaigns (e.g. community information, wall
posters), and health care facilities (e.g. doctors, information campaigns from hospitals)
(Bork-Huffer, 2012, 181). In a study done by Adelman, Essam, and Leonard in 2009,
there was evidence to show that households gained and evaluated different health care
facilities by watching and learning from their neighbors’ experiences, or by using social
learning skills (Dupas 2011, 15-16).
Unfortunately, the spread of information does not happen in areas where the
coverage of treatment is low because there “…is less opportunity to learn of its benefit”
(O’Donnell 2007, 2826). A study to research limitations in health care access within the
Saptari district of Nepal showed that most residents living in this community lacked
information on medicines and health care services and incentives (Daniel et al. 2012, 3).
Most importantly, information was not being disseminated in effective ways.
Reliability and reputability of the organization providing information is critical.
The community must trust the provider in order to want to receive health care and seek
out health care treatment from the respective source. Trust can be gained or lost by
observing the effectiveness of services. If the services provided are successful and high

13
quality, trust will be established (O’Donnell 2007, 2826). Alderman and the World Bank
have done studies that prove demand for health care will go down when quality
diminishes. A study in a rural region of India, done by Gwatkin with the World Bank,
showed a correlation between low utilization of a free, public health care facility and low
quality of health care being provided (O’Donnell 2007, 2081-2).
Members of one’s social network highly influence a sick person’s ability to access
health care. Research participants in a study in the Saptari district of Nepal emphasized
the importance of social capital in accessing health care. The utilization of social
networks through friends, family and relationships, were shown to be critical in gathering
information and support relating to health care, services, and financial help (Daniel et al.
2012, 3). One way support can be provided is by taking over the sick person’s chores,
work, or housework. Spouses mainly take over this responsibility, however, other family
members, such as parents and children, also help in this capacity. Less often, one’s
neighbors and friends take part in helping to alleviate the burden of work (Bork-Huffer
2012, 242).
Gender inequality is a major factor in reducing access to health care for females in
many economically developing countries, including Nepal (Sreeramareddy, Harsha
Kumar, Sathian 2013, 2). The Seva Canada Society and Seva Foundation found that
“women of all ages (including children) are more frequently exposed to causative factors,
such as infectious diseases and malnutrition…” yet they oftentimes have less ability to
get transportation to and from health care facilities, have access to less money, and are
more geographically isolated (Unite for Sight, 2000-2015(b), 1).

14
In economically developing countries, the root cause of gender disparities in
access to health care can be “traced to the low social status of women in much of the
developing world” (Unite for Sight, 2000-2015(b), 2). A study pertaining to eye care
produced by Geneau, Massac, Courtight, and Lewallen in Tanzania found “that men were
more likely than women to adopt a ‘sick role’. In contrast, women were more likely to
continue their routines through ‘adversity’ instead of emphasizing the need for [eye]
surgery” (Unite for Sight, 2000-2015(b), 2). In Humla district, gender inequality is
worsened by a high incidence of gender-based violence, triggered in part due to a wide
availability of Chinese alcohol (UNFCO 2013, 5).
Although females are at a disadvantage in their ability to access health care,
studies show that females attach a greater priority to child and maternal health care than
males (O’Donnell 2007, 2829). When compared to males, females spend more of their
income on health care for their children (Dupas 2011, 13). Although females are at a
higher disadvantage in accessing health care, they might seek out resources more than
men due to their values and “might respond different[ly] to information on the health
returns of various behaviors” (Dupas 2011, 13). Increasing the social conditions of
women, including changing gender roles and attitudes, is important in the fight for
providing global, accessible health care.
Although it is crucial that maternal, reproductive, and child health care be made
more accessible for females, the implementation of health care in this arena remains
challenging “within societies that restrict the public lives of women” (O’Donnell 2007,
2826). The cost of work replacement (both paid and unpaid) is a barrier in seeking health
care. A study was done by Banerjee, Duflo, Glennerster, and Kothari in 2010 that studied

15
the effects of health care seeking behavior when the cost of treatment was incentivized by
off-setting the cost of losing a day’s wage when receiving treatment. The study focused
on reliable immunization camps in Udaipur, India. Parents who brought their children to
one of the immunization camps received 1 kg of lentils per immunization administered.
This was equal to three-quarters day wage for the parent. The incentivized immunizations
grew immunization rates from 17% to 38% (Dupas 2011, 25).
Seeking health care for a mother is a burden to herself and also for her children.
When seeking health care for herself or one of her children, mothers often need to find
childcare for the rest of the children. This requires support from a social network. If the
health care facility is far away, the social request for childcare services is much greater
(MacKian 2003, 12-13). Childcare is a critical consideration for mothers and women who
take care of children (Ward 2009, 1591). Even if women require health-care services, the
competing demands of taking care of children can make it impossible to do so (Creel et
al. 1996, 3).
Socioeconomic Barriers that Prevent Accessible Health Care
In this project, I felt compelled to generate a better understanding of the impact of
socio-economic status (SES) on health care seeking behavior. I analyzed this in a fairly
fine-grained way, by looking at behavioral patterns of patients seen at one of the six
MMCs I analyzed. As Subedi argues, health issues in Humla , “among men [and] women,
cannot be separated from the larger social, cultural, economic, and political forces that
shape and constrain human life” (2010, 22). A patient’s SES proves to have a large effect
on both health care seeking behavior and the health of a population. “Poverty, which is a
result of social and economic inequality in a society, is detrimental to the health of

16
population. The outcome indicators of health (mortality, morbidity and life expectancy)
are all directly influenced by the standards of living of a given population” (Deogaonkar
2004, 1).
It is important that we take time to correctly understand the usage of SES as it will
be used in this paper. “SES is a difficult concept to define and to measure” (van
Bodegom et al. 2009, 68). It can be composed of different indicators, depending upon
whether the setting is in economically developed or developing countries. For this paper,
SES will be interpreted
as a hierarchical position that determines someone’s access to human or
material resources. SES largely influences health and survival in both
developing and developed countries. In developed countries SES is
mostly measured as a combination of education, income and occupation.
In developing countries however, especially in rural areas, most people
have little education and income tends to be fluctuant depending both on
the season and on the year and is not easily expressed in numbers. Also,
the SES in developing countries is largely dependent upon a relative,
social position in the community, clan or extended family and this is not
always reflected in property. [van Bodegom et al. 2009, 68]
Wilkinson suggests that it is not necessarily the deprivation of income, but instead
the distribution of income that matters. Multiple studies done across the globe have
revealed a strong association between excess mortality and income inequality. A study
done by Kennedy, Kawachi, and Prothrow-Stith, in the United States, showed that

17
income inequality directly affected the total mortality of the population. This study
measured income inequality using the ‘Robin Hood Index’. The ‘Robin Hood Index’ is a
measurement of the part of income that would need to be redistributed from the rich to
the poor in order to achieve economic equality. By this measure, a 1% rise would led to
21.7 excess deaths for every 100,000 people (Deogaonkar 2004, 1). It is well known and
documented that health disparities exist within Nepal due to inequality in socioeconomics
(Sreeramareddy, Harsha Kumar, Sathian 2013, 2).
Demery, in 2000, and Makinen et al., also in 2000, found evidence “…that access
to health services and the distribution of public subsidies favor richer, urban dwellers
over generally poorer, rural inhabitants” (Ensor, Cooper 2004, 1). Although the poor tend
to be the least healthy and need health care the most, they are usually the lowest in
utilization of effective health care services. Income disparities, which are greatest in
economically developing countries, lead to disparities in access to health care between
rich and poor. The poorest 20% of people in Nepal receive less than 10% of the public
health subsidy (O’Donnell 2007, 2822- 4, 2830). Research done in the Saptari district of
Nepal concluded that socioeconomic factors substantially contributed to limitations in
access to health care and poorer health status of Dalit communities (Daniel et al. 2012, 3).
A person’s SES affects their level of awareness in relation to health seeking
behavior. Lack of awareness is a direct barrier to seeking health care for oneself or one’s
children. India provides free immunizations to all children, yet still 2 out of 5 children are
not fully immunized. Pande and Yazbeck found that although the country provided free
immunizations, most female parents did not know about the benefits of immunization. A

18
large percentage of female parents who did understand the benefits of immunization did
not know where to go to receive vaccinations (O’Donnell 2007, 2826).
The ability to recognize illness is essential to seeking health care (Dupas 2011, 9-
15, 29). “…Cultural and educational factors may obscure the recognition of illness and
the potential benefits from health care…” (O’Donnell 2007, 2821). There is a direct
correlation between knowledge of illness and health care utilization. In order to demand
health care, there must be an ability to recognize illness and to recognize the benefits of
treatment. In a population where poor health is the norm, it is harder to recognize good
health as a viable option. Illness is more often reported in people who are wealthy than in
people who are poor. “The better off are more likely to seek care for a child when sick, to
take anti-malarials and antibiotics for pneumonia, and to receive inpatient care… The
unfortunate outcome [for the poor] can be the continued toleration of illness and disease”
(O’Donnell 2007, 2826).
Even when a person has full awareness of the availability of health care, the cost
of seeking health care treatment might be too great. Cost is oftentimes the most pressing
barrier to seeking health care (Unite for Sight 2000-2015(a), 1). Thus, even if health care
is recognized as needed, utilization might be suppressed because of economic constraints
(O’Donnell 2007, 2821). Gertler and Gaag saw successful health care utilization take
place within a poor population in Africa when certain factors were met: the ability to pay
with credit, reductions in travel time, and improvements in quality (O’Donnell 2007,
2825). “Individuals must be willing to use effective preventive and treatment
interventions and they must have the purchasing power to realize this desire” (O’Donnell
2007, 2827).

19
There is a positive relationship between one’s economic standing and the
utilization of heath care. Multiple studies have shown a correlation between prenatal care
and medically supervised deliveries with a rise in income. Steele, Diamond, Amin and
Gage, Sommerfelt, and Piani have shown a positive association between income and
child immunization through the use of multivariate analyses (O’Donnell 2007, 2825).
“Monetary costs of care [including the non-price costs of long distance travel] ensure that
income is an important determinant of health care utilization…” (O’Donnell 2007, 2825)
Cultural beliefs about allopathic medicine and the causes of disease also factor in
to one’s willingness to seek health care from western clinics and doctors. Fear of
procedures is daunting, especially when associated with visiting doctors or by short-term
medical interventions (Dupas 2011, 9-15). Social and cultural norms are oftentimes
reflected from attitudes that are deeply rooted in family traditions. These can produce a
low demand for modern health care. Social norms within groups are constantly evolving.
There is a correlation between a rise in education and a decline in seeking traditional
health care. Again, the socioeconomic environment influences social norms (O’Donnell
2007, 2826).
Lack of geographical access is a major barrier to receiving effective health care.
Distance has shown to have a greater effect on health care utilization in the poor than for
wealthy individuals. This makes sense due to poorer people living in areas with worse
road conditions, less available transportation, and greater social strains associated with
seeking health care. “In rural areas, the distances to health care facilities and the poor
condition of roads mean that time, effort, and cost required to arrive at the point of

20
delivery can be substantial. The evidence confirms the expected negative impact of health
care utilization” (O’Donnell 2007, 2826).
A cataract study conducted by Chang, Condon, Baker, Bloem, Savage, and
Sommer in rural Africa showed that distance to receiving health care was the most
important barrier in 1/3 of all patients (Unite for Sight 2000-2015(a), 1). A study in
Ghana showed that when the travel distance to a health care facility was cut in half, the
utilization rate almost doubled (O’Donnell 2007, 2826). “Lowering the barrier of distance
requires either taking people to services or services to people… road building is
expensive and is not under the control of health sector policymakers. More feasible are
schemes that lower the price of travel for health care or provide credit to cover travel
expenses” (O’Donnell 2007, 2830).
People living in urban areas generally have closer and better geographical access
to health care. Cities have the biggest concentration of health care provisions (O’Donnell
2007, 2083- 4). People in rural areas oftentimes have to travel far distances to receive
health care and also lack transportation services (Unite for Sight 2000-2015(a), 1). This
puts the rural region of Humla, Nepal at a greater disadvantage in being able to access
health care than people living in urban settings such as Kathmandu, Nepal.
Humla’s Weak Health Infrastructure
Humla’s population of 50,858 people is supported by only two hospitals and 26
health posts (of which 16 are mostly non-functioning) (UNFCO 2013, 8). The health
posts and hospitals frequently lack the appropriate equipment and trained health care
personnel (UNFCO 2013, 8). Health posts were weakened during the Maoist conflict
(1996-2006) through the ransacking of valuable materials (Citrin 2012, 74). Medical

21
posts usually consist of untrained staff, expected to treat patients with limited medical
education and a small amount of medicines.
All villagers in Humla district live in an extremely rural setting. Health posts are
usually not located or in working condition near most of these villages. Furthermore,
patients often find the medical posts to be temporarily or permanently closed, after
having traveled for an extensive amount of time (Citrin 2011, 34; Justice 1986; Sanders
and McKay 2013, 112).
Humla’s isolation from the rest of Nepal has attributed to the unavailability of
health care (Citrin 2011, 20). The mountainous topography of Humla has limited the
infrastructure of health care facilities (Sanders and McKay 2013, 109). In Nepal, there is
a major geographical advantage in seeking health care for people who live in or around
the Kathmandu Valley. The valley has more plentiful (though still insufficient) doctors
and health care resources. To reach Kathmandu from Humla, a walking trek and plane
flight is required. Most people who live in Humla cannot afford the transportation costs
of a plane flight (UNFCO 2013, 1).
Beyond distance, Humla has the highest elevation of any district in Nepal. Most
villages range in elevation between 3,000 to 5,000 meters above sea level (Digital
Himalaya’s Nepal Maps Collection 2014). Extreme gains and losses in elevation add to
an already long trek to seek health care. Long distance and large amounts of elevation
gain and loss would make this journey difficult for a sick person. Topography, inadequate
resources and shortage of trained medical personnel are all major factors in the
inaccessibility of health care within Humla district (Sanders and McKay 2013, 109).

22
Because Humla district is dependent upon agriculture for most of their food
security, seeking health care is highly contingent based upon the growing season.
Leatherman’s assumption is “if it is harvest or plowing season, time constraints on health
seeking are an even greater issue, often delaying treatment processes beyond the critical
period” (Sanders and McKay 2013, 112-3). Compensation for a day’s loss of work might
not be equivalent to the amount of impact that loss of fieldwork will produce. When an
individual’s health competes with the entire household’s economic outcome when faced
with the decision to work in the field or seek health care treatment, health concerns are
usually overlooked for the good of the family (Sanders and McKay 2013, 116).
The Rise of Mobile Medical Camps (MMCs)
Nepal was not colonized like many of its neighboring South Asian countries, and
it remained closed to outsiders and foreign health systems until the 1950s. Western
scientific medicine (called allopathic medicine in Asia) was not used in Nepal until a
revolution took place that restored the Nepalese monarchy and opened up borders
through the creation of an international airport in Kathmandu. Christian missionaries first
took advantage of the country’s opening to provide health assistance. By 1951,
government hospitals were available in Kathmandu (Justice 1986, 8). Before the 1950s,
health care was sought through family knowledge and the use of traditional healers. After
the opening of the borders, foreign drug companies started utilizing Nepal as an open
market for western drugs (Justice 1986, 8).
Although the Nepalese government has made progress in providing medical care
for its citizens, most health care advancements had been made in Kathmandu and other
cities, as opposed to rural areas where most of Nepal’s population still reside (Justice

23
1986, 9). Furthermore, as determined by the World Bank, scarce resources and
inefficiency has neglected to decrease major underlying causes of disease: “…poor
nutrition, polluted water, and lack of education in hygiene and sanitation” (Justice 1986,
9).1
Nongovernment organizations (NGOs) began taking over the government’s role
in providing health care for the poor and marginalized in the 1950s. The United States,
India, the Soviet Union, China and the World Health Organization (WHO) were among
the first external health care donors to Nepal (Justice 1986, 8). NGOs today, continue to
provide health care services to both rural and poor communities in Nepal. “NGOs provide
essential services that would otherwise leave masses of people without basic tools of
survival (e.g., sewage disposal, nutritional supplementation, and medicine)” (Sanders and
McKay 2013, 109).
Research addressing the politics of health care, health care development, and
health care provided by NGOs, has recently began to address their negative aspects
(Citrin 2012, 15). The role of short-term, traveling, health care-providing settings,
including MMCs, has been included in this critique. I will discuss a critical evaluation of
both donor agencies and NGOs within Humla district and MMCs, in particular, because
data for this project was obtained through this method of health care.
NGOs in Humla district have come under attack for many legitimate reasons.
Beyond the suspicion in motivation for funding, overlapping aid and under met needs,
time-related issues, and questions regarding potential benefits to providers instead of
1 An evaluation of the health care system in Nepal is critical in understanding why NGOs are
prevalent in the region. A detailed critique and history of development of the health care system
in Nepal is given by Judith Justice in “Policies, Plans, & People: Foreign Aid and Health
Development”.

24
people in need, there are theoretical reasons of critique. The ‘medicalization’ of hunger
is a major issue that needs addressing.
Funding for NGOs can come from politically motivated organizations. These
organizations might not address the most pressing concerns for the community being
served, but instead, might try to please the organization that provides the financial
backing (UNFCO 2013, 13, Citrin 2012, 18). Donor agencies might have ties associated
with funding that can prove more harmful than helpful to the recipient. For example,
“USAID is the largest bilateral donor of health aid to developing countries, including
Nepal. Its policy guidelines originate in the U.S. Congress, the U.S. Department of State,
and the Policy Division of USAID. The agency is therefore accountable to all three
levels” (Justice 1986, 26). Within an agency as large and diversified in its interests as
USAID, it’s hard to tell whom the agency is truly trying to benefit.
Many times, villagers needs and expectations are completely forgotten, and
instead plans are implemented based upon what the donor agency thinks is appropriate
(Justice 1986, 33). Therefore instead of being fully accountable to the recipient’s needs,
the donor organization is first and foremost accountable to its origins, then to the
recipient. Furthermore, to further complicate recipient needs, donor agencies such as
USAID hire advisors from private companies, which could have different objectives than
even the donor agency (Justice 1986, 28).
Currently, there are more than a hundred NGOs in the district of Humla, Nepal.
Better services could be provided if work was consolidated within the organizations
instead of duplicated between them. Aid is overlapping in many areas (Justice 1986, 9)
and not meeting needs in many others. Even with the vast amount of NGOs available in

25
Humla district, people still fail to have their most basic health care needs met (Sanders
and McKay 2013, 109-110).
Furthermore, competition among donors can create tension for the recipient who
is caught in the middle of a funding feud. These battles could be avoided if donor
agencies assisted programs created by the Nepalese government, instead of creating their
own (Justice 1986, 33). “…Too many donors and too little coordination” (Justice 1986,
33) can lead to massive amounts of confusion and lack of help for the recipient.
Many donor-led projects have to include a time-line and objective to be
completed within just a short period of time. Oftentimes the stated objectives are too
large or unreasonable to complete. However, to continue receiving aid, material results
must be produced. This can lead to falsifying results, or lead to the creation of hard
outcomes, even if the falsified outcomes are not what are most beneficial for the
recipients (Justice 1986, 27-32).
Funding for projects with short time-lines and hard outcomes lead to a continuous
repetition of unfinished and unnecessary projects. Many NGOs leave after completing a
faulty and short-term project, even when infrastructure has not been put into place. Due
to large attrition rates after the completion of small projects from many donor
organizations, there is a feeling of resentfulness and distrust towards NGOS from the
recipients of these projects (Sanders and McKay 2013, 112).
MMCs are known in the NGO world as providing short-term care. Even in their
title they profess to be mobile entities. An MMC’s main objective is to provide temporary
health care within a short period of time, then move on to other areas of need. This idea

26
questions both the effectiveness of health care being offered, and also, the ability to
provide continuous health care for individual persons.
David Citrin, Nancy Scheper-Hughes, and Ivan Illich question the
‘medicalization’, or seemingly endless supply of drugs, which are thrown at an issue that
might be more benefitted by addressing the root cause- a food crisis (Citrin 2012, 17;
Illich 1975, 31; Scheper-Hughes 1992, 203). Virchow wonders whether bettering social
conditions is the more important task at hand (Citrin 2012, 17)? Their argument is that
MMCs provide a venue which “strip[s] the conditions that foster poverty, scarcity,
sickness, and hunger of their human origins and [turn] them into problems solvable by
dispensing medications or food in the short-term” (Citrin 2012, 18).
Furthermore, the term mobile medical camp might be a misnomer. Even though
MMCs are mobile, many people still have to travel long distances to reach them. Results
of travel times can be seen in the results section in Table 14.
Despite these critiques, NGOs and MMCs continue to exist and provide care that
would otherwise not exist. “Insufficient resources, inappropriate allocation, and
inadequate quality are major impediments to the delivery of effective health care that
reaches the poor” (O’Donnell 2007, 2825). The problem of access to health care is two-
sided: supply and demand. MMCs in Humla, Nepal, as well as the rest of the world, are
striving to perfect the demand-side of health care. The reality is that many economically
developing countries, including Nepal, depend on support from NGOs to provide health
care for its citizens (O’Donnell 2007, 2829).
MMCs are used around the world because they have several advantages. They can
provide “…autonomous functioning, rapid reacting, mobility and universality, [and]

27
availability…” (Glu, et al. 2012, 128). These health care facilities can provide medical
care even in the most remote settings where there is a lack of health infrastructure (Glu,
et al. 2012, 128). There are an estimated 1,500 MMCs in the United States alone, serving
the most vulnerable population of low-income, high-risk patients. Even in the United
States, these MMCs provide health care to a population that would otherwise not receive
services (Hill, et al 2014, 261).
MMCs are even being used to help fight AIDS in Sub-Saharan Africa, where 3/4s
of the world’s AIDS population resides. MMCs in this setting will be used to treat and
track AIDS patients and rates in rural areas. They are able to provide needs assessments
“…and deploy limited resources accordingly. In the future, such a network could also
play a vital role in distributing antiretroviral drugs and eventually a vaccine” (Open
Architecture Network 2012, 1).
The World Health Organization believes that the “lack of availability [of health
care facilities and resources] is the root of the problem in many instances” (O’Donnell
2007, 2821). Due to the mountainous terrain of Humla, an infrastructure of health care
buildings was either never built or has been poorly staffed, equipped, and maintained
(Sanders and McKay 2013, 109). MMCs are mobile and have the ability to provide health
care without a large amount of infrastructure.
MMCs have the ability to provide effective and quality health care, fulfilling
requirements for the supply end of the problem of access to health care. Demand-side
barriers can be addressed once supply-side barriers are controlled (O’Donnell 2007,
2820). The goal of MMCs in the long run is to provide medical treatment that is not

28
available through any other means, and to also increase self-sufficiency in the most
vulnerable populations around the globe (Subedi 2010, 30).
Besides being able to provide health care, most NGOs provide health care for free
or at major discounts. This greatly increases the amount of people who can access health
care. It relieves one of the financial barriers of accessing health care for poor people.
Price-elasticity of health care has a major effect on demand for the service. When health
care prices are lower, the demand for health care is higher. A study by Banerjee, Duflo,
Glennerster, and Kinnan in 2009 showed that most people in economically developing
countries spend a large portion of their resources on obtaining health care (Dupas 2011,
2-3). In 2006, Van Doorslaer, O’Donnell, and Rannan-Eliya showed that health care
expenditures further exacerbated economic conditions in already-impoverished
households (Dupas 2011, 2).
MMCs may reduce morbidity and mortality and meet an unmet health need in
rural communities. Specifically, MMCs provide immunizations, preventive care, and
health care technologies to a population that would otherwise not receive them. Again, a
major barrier to health care is the cost of the treatment. Guyatt, Ochola, and Snow have
shown that most households state their main reason for not using health care treatment is
because of financial costs. The use of preventative technologies by MMCs has been
shown to reduce child mortality and morbidity by large numbers (Dupas 2011, 4-5).
NGOs and MMCs are filling a gap in providing health care that the government
cannot or will not provide. Preventive care in economically developing countries, which
is supplied through the public sector, is often sparse, not available, or not fully
functioning. A study by Banerjee, Duflo, Glennerster, and Kothari, in 2010, revealed that

29
45% of public health care workers in Udaipur, India were absent from their stationed
health posts on any given day (Dupas 2011, 5-6). Absent health care workers from health
posts has been shown to reduce provider reliability and patient confidence in the quality
of care. Provider reliability has been proven to increase health care accessibility. Patients
will be more willing to travel if quality health care is provided. In an ideal fashion and for
certain services, MMCs can provide reliable, consistent, and well-advertised health care.
In Udaipur, India, child immunization rates increased from 49% in an unreliable health
care setting to 78% in a reliable health care setting (Dupas 2011, 6).
MMCs provide rural areas with treatment for remedial care and information for
health care prevention. “…Lack of information on illness prevention or on the
effectiveness and cost-effectiveness of preventative behaviors” (Dupas 2011, 9) is a
barrier to seeking health care. Numerous studies have shown that information given to
households in relation to specific preventive techniques, promotion of good hygiene
practices, and remedial health behavior, affects health care choices and treatment (Dupas
2011, 9-11). “Households in developing countries often lack information on the returns to
investing in preventive behavior [which is unfortunate because] health behavior is quite
responsive to information” if given by a reputable source (Dupas 2011, 12).
Many government-funded, public health care facilities often are not utilized
because of the poor quality of health care they provide. Primary care clinics claim to
provide benefits for their communities, however, a review by Filmer, Hammer, and
Pritchett for the World Bank showed mixed evidence on whether primary care clinics
were effective at all in their impact on population health (O’Donnell 2007, 2821). NGOs
might be able to help impact population health by sending reputable and reliable MMCs

30
to distribute information. MMCs can remain reputable and reliable by conducting QI
(quality improvement) studies. They need to be consistent and continuous in gathering
data, not only pertaining to patient health, but also to patient socio-demographics and
socioeconomics. It is important that patient input be gathered and taken into
consideration in order to provide the best possible care.
Health related NGOs are making efforts to provide more holistic and permanent
care for their recipients. The NGO that collected the data used in this thesis is working to
produce better monitoring systems for patient follow-up care. Patients who need long-
term care are monitored using a patient database with contact information. Follow-up
testing for how well this was accomplished is currently in process (Kimber McKay,
personal communication, October 2014). Compilation of this database including 1,138
participants was in response to critiques of short-term medical camps by scholars and
practitioners, and to villagers’ stated need for more extensive education, referral, and
follow-up care.
Data Acquisition and Preparation
The data that was used for this thesis was extant data in a quality improvement
(QI) study completed by Nepali citizens working for an NGO. I was commissioned to
help analyze the existing data from this respective NGO. I was handed this de-identified
data and did not collect this data. Therefore, the data gathered did not undergo IRB
review or approval.
Two Nepali doctors collected and entered data from 1,138 participants who
attended one of six MMCs in Humla district of Northwestern Nepal in December of
2013. All patients attending the MMC were seeking remedial health care. Remedial

31
health care restores the health of the patient when there is an illness, as opposed to
preventive health care, which reduces the risk of bad health and illness (Dupas 2011. 7).
Surveys were given to all patients. If the patient was a child the survey was given
to their parent. The information collected in this case included the child’s reason for
seeking treatment but the socioeconomic measures, socio-demographic measures, health
care measures, and measures of health care accessibility of the parent.
The data were collected in the form of hard copy for every patient who attended
any of six MMCs and entered into the Nepali language. There was some translation from
Tibetan into Nepali in the Buddhist villages by members of NGO camp staff, but no
English translation occurred in the field. Locations of data collection were six sites within
the Humla district of Nepal: Chauganphaya, Dandaphaya, Kermi, Muchu, Syada, and
Yalbang.
After the camp, the physical data were translated into English and Excel, at the
same time. The data collectors were literate villagers with high school educations and the
data were digitized by the chair of the Department of Social Work at Classic College in
Kathmandu, Nepal. I received the database in Excel format and transferred the data into
SPSS format, concurrent with the organization needed for the respective analyses.
Myself, a second research assistant, and the NGO’s director of research performed
quality checks in Excel and SPSS.
Limitations in Data Acquisition
Data limitations were present because data were based upon survey data collected
by other workers from an NGO. In order to produce a fuller examination of
socioeconomic influences on health care seeking behavior, additional data would have

32
been required. Specific details about the severity of patient medical conditions could
provide data for fuller SES analyses. Furthermore, qualitative data for variables analyzed
with SES, such as healthcare indicators (amount of time since previous treatment was
received, type of health care facility visited for previous treatment, location of previously
received treatment, person who provided work replacement while patient was seeking
health care, whether children were brought with patient or left at home, person who
provided childcare while patient was seeking health care) would help provide a fuller and
more robust analysis. However, because the dataset used for this thesis was given to me
with set variables, I conducted an analysis of socioeconomic influences within the given
dataset.
I would also like to acknowledge the people who were too sick to walk to an
MMC to receive health care. This dataset did not include the sickest people who were
unable to travel by foot to an MMC or the poorest people, who could not afford to lose
work by taking time to walk to the MMC and receive health care.
Analysis Methodology
This thesis included two sub-projects. The first project used SPSS (Statistical
Package for the Social Sciences) to produce both descriptive and inferential analyses.
This project’s goal was to assess the contribution of SES to health care seeking behavior.
This project tested the hypothesis that SES has an effect on one’s health care seeking
behavior. Variables tested by analyses in SPSS included SES indicators, socio-
demographic indicators, health care access indicators, and sickness indicators.
Socioeconomic status (SES) indicators: Socioeconomic measures were gotten from
each patient based upon a threefold (high/medium/low) self-identifying method. Levels

33
of SES are identified by the amount of land one has, the amount of animals one has, and
food security (Humla District Development Committee 2000, 18-19). Humla district is a
primarily egalitarian. Eighty-one percent of households are income dependent on
agriculture and 12% are income dependent on wage labor (Humla District Development
Committee 2000, 18). This rapid appraisal method of identifying SES is an
anthropological method “which uses qualitative measures of SES and is designed to rank
or stratify participants in wealth categories” (van Bodegom et al. 2009, 69). This method
has shown to be accurate in representing one’s actual SES through comparison with other
forms of SES-gathering methodology, including the Demographic Health Survey (DHS)
wealth index and interview-reported wealth (van Bodegom et al. 2009, 67).
Socio-demographic indicators: Socio-demographic indicators were compared against
SES to ascertain any relationships. Socio-demographic indicators included age, gender,
marital status (single, monogamous, polygynous, polyandrous (a marriage system in
which a woman marries a set of brothers), monogamous but used to be polyandrous),
number of adults living in household, village of residence, and village where respondent
was born.
Health care access indicators: Variables were measured which indicated one’s level of
accessibility to health care. The amount of time traveled to receive health care (in
minutes) was measured. All patients seen at one of six MMCs traveled by foot to receive
health care. Trails in Humla district are not built for transportation other than walking,
and villagers are too poor for other forms of transportation. The amount of time since
previous treatment was received (in months), type of health care facility visited for
previous treatment (e.g., none, health post, health camp, hospital, traditional,

34
unspecified), and location of previously received treatment were measured. The person
who provided work replacement while patient was seeking health care (e.g., no one, self,
spouse, affine (non-blood relation), consanguine (blood relation), non-relatives, other
family members, child went to school) was also provided. Work replacement was
provided for everyone, regardless of whether they had to travel from another village or
received health care at an MMC in their same village of residence. Whether children
were brought with patient or left at home was measured, the person who provided
childcare while patient was seeking health care (e.g., no one, self, spouse, affine,
consanguine, non-relatives, other family members, child went to school) was measured,
and village where health care was sought was measured.
Sickness indicators: One sickness indicator was measured and compared with SES in
search of a relationship. This variable included chief medical complaint/ reason for
attending MMC (e.g., fever, head pain, body pain, respiratory, vision impairment, GI
tract, genital, reproductive or STI related, tooth or mouth pain, ear ache or hearing
impairment, allergy or itching, wound, other, which included dizziness, shivering, heart
pain, worms, nose pain, throat pain).
Descriptive Statistical Analysis
The analyses conducted were based upon nominal and ratio data. I performed
frequency analyses for each nominal variable being tested: SES, gender, marital status,
village of residence, village where respondent was born, type of health care facility
visited for previous treatment, location of previously received treatment, person who
provided work replacement while patient was seeking health care, whether children were
brought with patient or left at home, person who provided childcare while patient was

35
seeking health care, village where health care was sought, and chief medical complaint/
reason for attending MMC. I performed descriptive statistical analyses for all ratio
variables being tested: age, number of adults living in household, amount of time traveled
to receive health care, and amount of time since previous treatment was received.
Prior to the inferential analysis performed, I conducted tests upon the data to
investigate their quality. I produced a test for significant outliers. I performed a
distribution analysis on all relevant variables by finding the kurtosis and skewness.
Results from this test influenced the use of either parametric “…statistical procedures that
rely on assumptions about the shape or form of the probability distribution from which
the data were drawn” or non-parametric parametric analyses “…statistical procedures that
do not rely on assumptions about the shape or form of the probability distribution from
which the data were drawn” (Hoskin N.D., 1). To produce more robust results with the
highest statistical power, I hoped that results would be normal and parametric tests could
be performed (Garth 2008, 4-5). Prior to an analysis of comparison of means, I performed
Levene’s test for homogeneity of variances to assess the assumption that the populations
of samples were equal.
Inferential Statistical Analysis
I conducted two types of inferential analyses: one-way ANOVA (analysis of
variance) and chi-square test. I conducted a one-way ANOVA analysis for both socio-
demographic variables, SES, sickness indicators, and health care access indicators (Aerd
2013, 1). I performed analyses to test whether SES determined the number of adults
living in the patient’s household, whether SES determined if and when previous
treatment was sought for remedial illnesses, and if SES determined the amount of time

36
patients traveled to receive health care. I conducted a one-way ANOVA analysis after
assumptions in my data were validated (Aerd 2013, 1). The dependent variables (number
of adults living in household, amount of time since previous treatment was received, and
travel time needed to reach MMC) were continuous and measured at the ratio level. The
independent variable (SES) consisted of three categorical and independent groups: low,
medium, and high. There was no relationship between the independent variables, either
within or between groups. These results allowed for independence of observations (Aerd
2013, 1).
I conducted a chi-square test to determine whether there was a statistically
significant association between SES and nominal variables, such as socio-demographic
indicators, health indicators, and health care access indicators. Socio-demographic
indicators included village where respondent was born and village of residence, patient
gender, and marital status. Health indicators included chief medical complaint/ reasons
for attending MMC. Health care access indicators included type and place of treatment
already received, work replacement and childcare, and respective MMC where patient
received health care.
Spatial Examination of Health Care Seeking Routes
In the second project, I used ArcGIS (geographic information system) and Google
Earth to produce a map that showed walking routes between GPS-located patient villages
and MMCs. This map calculated the distance that was needed to travel between villages
and MMCs. For each route I created a distance and elevation profile.
From the dataset, I matched participants from their village of residence to the
respective MMC they attended. Using aerial photographs from Google Earth, I located

37
the six MMCs and all villages of residence. I mapped the GPS locations using ArcGIS.
Then I mapped the most commonly used routes from all villages to the six MMCs using
Google Earth route. The ending result included routes from GPS locations of six MMCs
and 14 villages.
The goal of this project was to show the distance, as well as gain and loss in
elevation, required to access health care for villagers within Humla, Nepal. This route
map could be used against the MMC database in measuring costs of travel to determine
distance decay (the decrease in utilization with distance) (Mueller et al. 1998, 878).
Results of Statistical Analyses and Spatial Construction of Routes
Table 1 shows the results of a frequency analysis of chief medical complaint at all
MMCs for both females and males. Although there were only 1138 patients, many
patients reported multiple injuries and medical complaints. Body pain in both males and
females was the highest medical complaint.
Table 1: Patient Chief Medical Complaint
Medical Complaint Patient Count Percentage Female Percentage Male Percentage
Body Pain 511 28% 339 28% 172 29%
Respiratory 294 16% 182 15% 112 19%
GI Tract 286 16% 212 17% 74 12%
Head Pain 223 12% 170 14% 53 9%
Vision Impairment 191 11% 123 10% 68 11%
Other 172 9% 102 8% 70 12%
Mouth Pain 66 4% 48 4% 18 3%
Ear Pain/ Hearing Impairment 46 3% 19 2% 27 5%
Genital, STI, Reproductive 24 1% 24 2% 0 0%
Total 1813 100% 1219 100% 594 100%
Table 2 shows the results of a frequency analysis of patient SES for both females
and males. Although there were 1138 patients, some did not provide a self-report of SES.
The highest category of SES was the middle level, which indicated that most patients
considered themselves not to be rich or poor, but somewhere in between.
Table 2: Patient Socioeconomic Status

38
Level of SES Patient Percentage Female Percentage Male Percentage
Low 174 15.7% 116 10.5% 58 5.2%
Middle 900 81.3% 602 54.4% 298 26.9%
High 33 3% 26 2.3% 7 0.6%
Total 1109 100% 744 67.2% 363 32.8%
Tables 3a and 3b show the results of a frequency analysis of patient gender and
age. Results conclude that more female than male patients attended MMCs. The highest
age group range to seek health care at an MMC was from ages 21 to 30.
Table 3a: Patient Gender and Age in Years (Age 1-50)
Gender Age
1-10 Percent 11-20 Percent 21-30 Percent 31-40 Percent 41-50 Percent
Female 3 43% 99 70% 202 79% 175 76% 109 62%
Male 4 57% 42 30% 53 21% 54 24% 68 38%
Total 7 100% 141 100% 255 100% 229 100% 177 100%
Table 3b: Patient Gender and Age in Years (Age 51-90)
Gender Age
51-60 Percent 61-70 Percent 71-80 Percent 81-90 Percent Total Percent
Female 96 56% 58 54% 13 41% 3 38% 758 67%
Male 75 44% 49 46% 19 59% 5 62% 369 33%
Total 171 100% 107 100% 32 100% 8 100% 1127 100%
Table 4 shows the results of a frequency analysis of patient SES and respective
MMC attended. The MMC at Chauganphaya treated more patients than any other MMC.
Table 4: Patient Socioeconomic Status and MMC Attended
MMC Attended SES
Low Percentage Medium Percentage High Percentage Total Percentage
Chauganphaya 91 52% 366 41% 6 18% 463 42%
Dandaphaya 58 33% 188 21% 7 19% 253 23%
Kermi 0 0% 54 6% 0 0% 54 5%
Muchu 1 0% 47 5% 1 3% 49 4%
Syada 15 9% 186 21% 18 55% 219 20%
Yalbang 8 6% 57 6% 1 3% 66 6%
Total 174 100% 902 100% 33 100% 1109 100%
Tables 5-10 show the results of a frequency analysis for each MMC and the
villages of residence that most often frequented the MMC. These results allowed us to

39
better understand the routes that patients traveled to seek health care. Results from this
frequency analysis were indicative of proper placement of MMC locations for residents
of the Humla district. Results showed that the MMC at Chauganphaya was most
frequented by villagers living in Chauganphaya, the MMC at Dandaphaya was most
frequented by villagers living in Dandaphaya, the MMC at Kermi was most frequented
by villagers living in Kermi, the MMC at Muchu was most frequented by villagers living
in Muchu, the MMC at Syada was most frequented by villagers living in Syada, and the
MMC at Yalbang was most frequented by villagers living in Yalbang. These results were
expected. If results showed that MMCs were not providing the largest percentage of their
health care to residents within their own village, this would be indicative of providing a
misplaced MMC. These results acknowledge proper placement of MMCs provided by the
NGO in the Humla district.
Table 5: MMC (Chauganphaya) Attendance Based Upon Village of Patients’ Residence
Village of Residence Number of Patients Percentage
Chauganphaya 127 27%
Kholsi 82 17%
Dharapori 62 13%
Hepka 61 13%
Dinga 48 10%
Pamlatum 32 7%
Gadapori 20 4%
Syada 18 3%
Other 27 6%
Total 477 100%
Table 6: MMC (Dandaphaya) Attendance Based Upon Village of Patients’ Residence
Village of Residence Number of Patients Percentage
Dandaphaya 226 88%
Tulin 15 6%
Dharapori 6 2%
Chauganphaya 4 2%
Other 5 2%
Total 256 100%
Table 7: MMC (Kermi) Attendance Based Upon Village of Patients’ Residence
Village of Residence Number of Patients Percentage

40
Kermi 52 96%
Chyaduk 2 4%
Total 54 100%
Table 8: MMC (Muchu) Attendance Based Upon Village of Patients’ Residence
Village of Residence Number of Patients Percentage
Muchu 30 60%
Dumkot 11 22%
Yari 8 16%
Thawang 1 2%
Total 50 100%
Table 9: MMC (Syada) Attendance Based Upon Village of Patients’ Residence
Village of Residence Number of Patients Percentage
Syada 194 85%
Sata 13 6%
Kholsi 12 6%
Yangu 5 2%
Other 4 1%
Total 228 100%
Table 10: MMC (Yalbang) Attendance Based Upon Village of Patients’ Residence
Village of Residence Number of Patients Percentage
Yalbang 34 49%
Yangu 20 29%
Chala 16 22%
Total 70 100%
Table 11 shows a frequency analysis of childcare decision making for patients
who traveled from their village of residence to one of six MMCs to receive health care.
Patients were asked whether they brought their children or left them at home. Results
showed that most parents left their children at home.
Table 11: Patient Childcare Decision Making
Frequency Percentage
Left Children at Home 757 70.7%
Brought Children 312 29.2%
Table 12 shows a frequency analysis of childcare decision making for patients
who traveled from their home village to one of six MMCs to receive health care. Out of
the patients who left their children at home (see Table 11) patients were asked to give
their childcare provider (given in the form of the relationship to health care seeking

41
parent). Options included no one, spouse, affine, consanguine, and other (unspecified).
Results showed that most parents left their children at home with no one watching them.
Table 12: Patient Childcare Provider
Frequency Percentage
No one 416 52.2%
Spouse 235 29.5%
Affine 31 3.9%
Consanguine 99 12.4%
Other 28 3.5%
* Multiple answers could have been given, so numbers don’t add up to equal 757 (Table 11, Left Children at Home)
Table 13 shows a frequency analysis of work replacement decision making for
patients who traveled from their home village to one of six MMCs to receive health care.
Patients were asked to give their work replacement provider (given in the form of the
relationship to patient). Options included no one, spouse, affine, consanguine, and other
(unspecified). Results showed that the patient’s spouse usually provided work
replacement for the patient.
Table 13: Patient Work Replacement
Frequency Percentage
No one 165 14.8%
Spouse 517 46.2%
Affine 182 16.3%
Consanguine 383 34.3%
Other 8 .7%
Table 14 shows the descriptive statistics for amount of time traveled to MMC (in
minutes) for 1126 patients who traveled from their home village to one of six MMCs to
receive health care. The results excluded 1 major outlier. Results indicated that the mean
amount of time traveled to MMC was 40.9 minutes, the maximum was 720, and the
minimum was one minute.
Table 14: Amount of Time Traveled to MMC (in minutes), excluding outliers
Valid 1126
Missing 16
Mean 40.9423
42
Median 15
Mode 5
Std. Deviation 66.3517
Minimum 1
Maximum 720
In order to conduct an ANOVA analysis, I produced a test for significant outliers
on all dependent variables so I could extract any potential outliers that could have a
negative effect on the ANOVA analysis. Without outliers the validity of the results would
be maintained. Dependent variables tested for significant outliers included the number of
adults living within the respondent’s household, when previous treatment was received
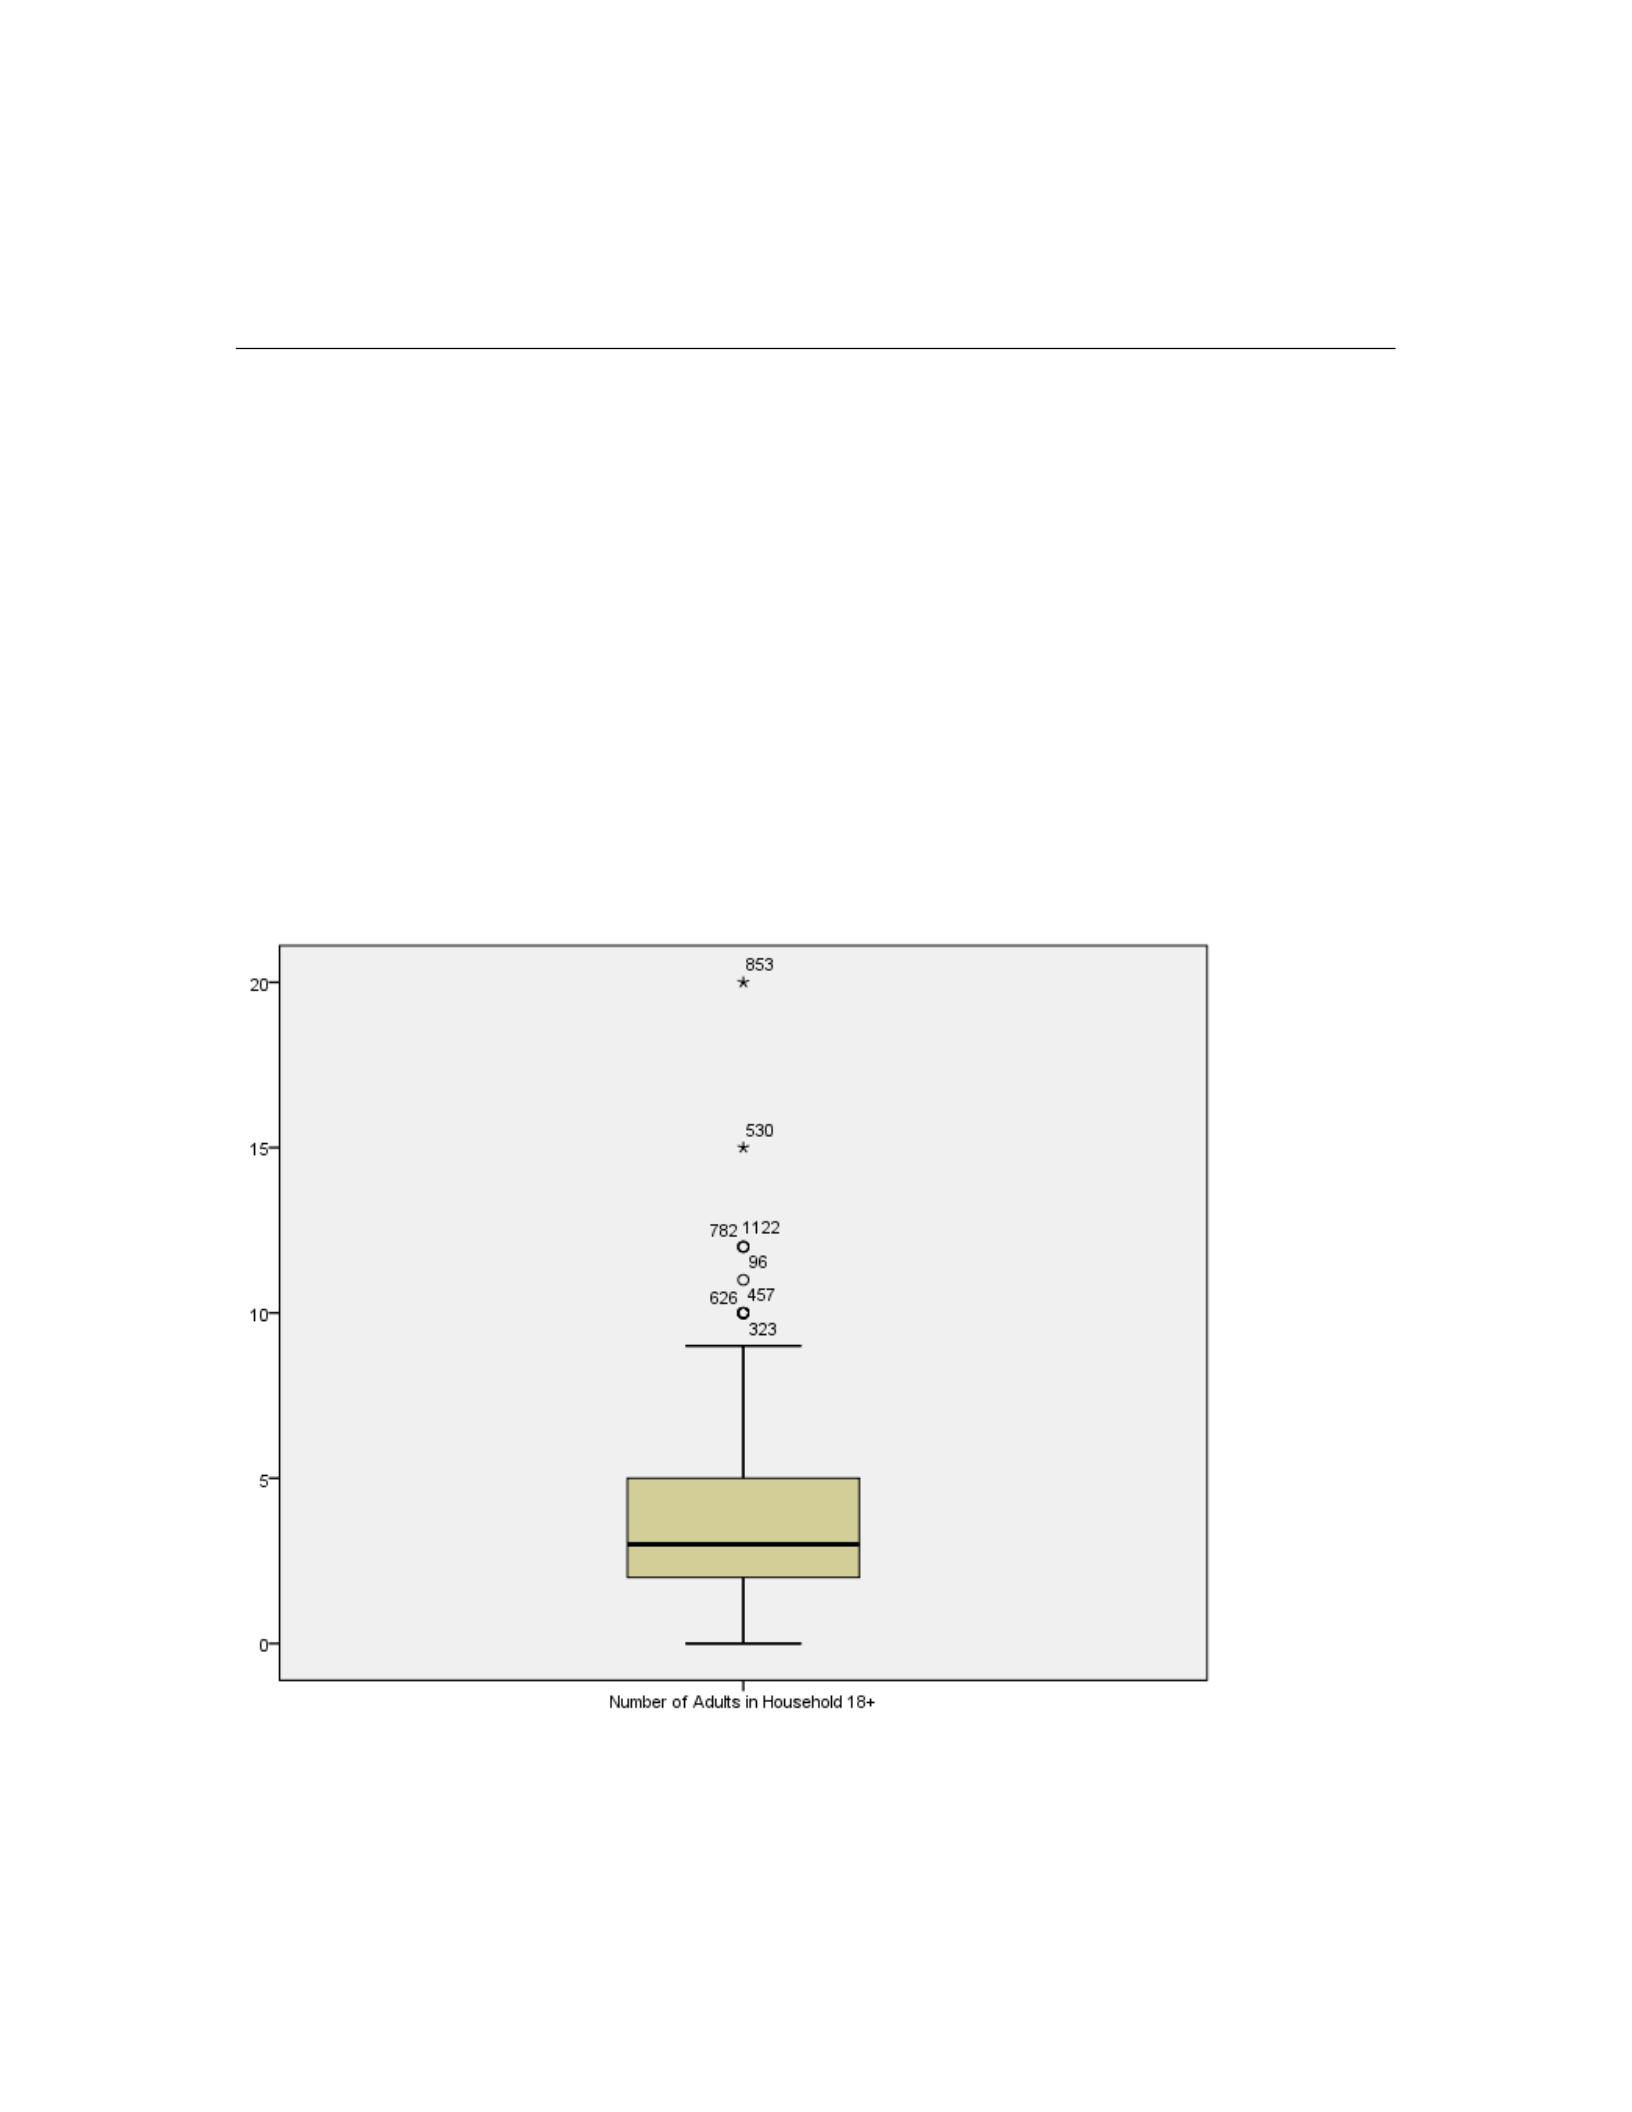
(in months), and amount of time required to travel to the MMC (in minutes). Figures 2- 4
show results. There were no outliers within the three dependent variables.
Figure 2: Test for Outliers within Number of Adults in Household

43
Figure 3: Test for Outliers within Amount of Time Traveled to MMC (in minutes)
Figure 4: Test for Outliers within When Previous Treatment was Received (in months)

44
I conducted a test for normal distribution on the dependent variables, based upon
the assumption that an ANOVA analysis needs to be performed on a normally distributed
dataset. I conducted a test to determine the skewness and kurtosis of distribution on all
three dependent variables used in the one-way ANOVA analysis. Dependent variables
included the number of adults living within the respondent’s household, when previous
treatment was received, and amount of time traveled to MMC.
Table 15 shows results. The skewness (which signifies how symmetrical the
distribution is) must equal 0 to be symmetrical and have a normal distribution. These
values are shown below to be substantially asymmetrical. The values have a positive
skew, which means the distribution is asymmetrical with a long tail to the right. The
kurtosis values are well above the expected kurtosis of 0, which means they have a
positive kurtosis. Although the dependent variables were not shown to be normally
distributed, my decision to use a parametric test was influenced by the sort of data being
analyzed. Even though these distributions didn’t seem to be normal and an assumption
was violated, the ANOVA test still seemed the most appropriate test used to analyze a
ratio variable against a nominal variable.
Table 15: Test for Normal Distribution of Dependent Variables
Skewness Kurtosis
Number of Adults in Household (above age 18) 1.541 6.083
When Previous Treatment was Received (in months) 33.044 1103.279
Amount of Time Traveled to MMC (in minutes) 2.074 4.019
Table 16 shows the results from Levene’s test for homogeneity of variances for
SES and all dependent variables tested within the ANOVA analysis. For all variables
except the number of adults in household sig > .05, which meant that the obtained
differences in these sample variances were not significantly different. For variables with

45
a significance level greater than .05, the null hypothesis of equal variances could not be
rejected. I therefore concluded that there was no difference between the variances in the
population. Because of this parametric tests could be performed on the samples.
However, because the significance level was lower than .05 within the number of adults
in household, the null hypothesis had to be rejected. This meant that a one-way ANOVA
analysis could not be performed on the number of adults in each household because the
obtained differences in the sample of variances was significantly different.
Table 16: Homogeneity of Variances for SES
Levene Stat Sig
Number of Adults in Household (above age 18) 3.569 .029
When Previous Treatment was Received (in months) 1.794 .168
Amount of Time Traveled to MMC (in minutes) .182 .834
Table 17 shows the results of the descriptive statistics for a one-way ANOVA.
This analysis tested whether number of adults living in household, when previous
treatment was received, and amount of time traveled to MMC differed based upon level
of SES. These three tests were included because I was expecting people with a higher
SES to have a lower number of adults living in each household, have a greater frequency
of treatment, lower amount of time since last treatment was received, and have a lower
amount of time traveling to MMCs due to greater options for transportation.
Table 17: Descriptive Statistics of one-way ANOVA for SES
Independent Variables SES
Low Medium High
Number of Adults in Household Mean: 3.2 Mean: 3.8 Mean: 3.3
Minimum: 0 Minimum: 0 Minimum: 0
Maximum: 8 Maximum: 20 Maximum: 9
When Treatment was Received (in months) Mean: 13 Mean: 8.4 Mean: 3.9
Minimum: .1 Minimum: 1 Minimum: .1
Maximum: 120 Maximum: 180 Maximum: 12
Amount of Time Traveled to MMC (minutes) Mean: 45 Mean: 64 Mean: 45.2
Minimum: 1 Minimum: 1 Minimum: 2
Maximum: 720 Maximum: 1500 Maximum: 300

46
Table 18 shows the results of a one-way ANOVA analysis for SES and all
dependent variables (except for number of adults in household, which could not be
analyzed using an ANOVA analysis because it did not pass Levene’s test for
homogeneity of variances). The test indicated that there were no statistically significant
differences in the mean of when treatment was received and amount of time traveled to
MMC. Both significance levels were greater than 0.05. I expected that people with higher
SES would be more likely to seek treatment more frequently. The finding suggested that,
irrespective of wealth status, there was no difference in the frequency of treatment
sought. Similarly, I expected that people with higher SES would be more likely to spend
less time traveling to an MMC, as they might be able to afford transportation services
other than walking. However, again, irrespective of wealth status, there was no difference
in the amount of time required to travel to an MMC.
Table 18: Results for One-way ANOVA Analysis for SES and Dependent Variables Tested
Dependent Variable Sig
When previous treatment was last obtained .214
Amount of time required to travel to MMC .932
I performed multiple Pearson chi-squared analyses on the SES of patients to test
for an association between SES and other variables. Analyses tested the null hypotheses
that SES would not be related to or have a relationship with any of the following
variables: marital status, patient gender, chief medical complaint, childcare decision
making, work replacement, type and place of previous treatment received, respondent’s
village of birth, residence, and which MMC the patient attended. Table 19 shows the
results of statistically significant variables that were shown to have a relationship with
SES.

47
I was curious to see whether there would be a relationship between SES and
people of differing marital statuses or chief medical complaint. I would have expected to
see a relationship between SES and patient gender, as females in most of Nepal generally
have a lower SES than males. Results showed no statistically significant relationship
between SES and marital status (p= .796), patient gender (p= .355), or chief medical
complaint (p= .088).
I would have expected to see an relationship between SES and childcare decision-
making. I predicted that people with a higher SES would be more able to attend an MMC
because it would be easier to find or hire childcare with a higher SES. I tested the null
hypothesis that SES and the decision to leave children at home or bring them to the MMC
were not related using a chi-squared analysis. The hypothesis was rejected because p<
.05. However, I also tested the relationship between SES and the provider of childcare
using a chi-squared analysis. This relationship was not significant (p>.05). A relationship
was proven between SES and whether the patient brought their children to the MMC or
left them at home. However, there was not a relationship between the provider of
childcare (spouse, affine, consanguine, non-relatives, and other unspecified family
members) and SES.
I expected to find relationship between SES and work replacement. I assumed that
people with a higher SES could afford to find or hire work replacement easier than
people with a lower SES. The results, shown in Table 19, provide evidence for a
relationship between SES and work replacement.
I expected to find a relationship between SES and type and place of previous
treatment received. I assumed that people with a higher SES would have traveled further

48
to seek medical treatment, and would also have sought westernized treatment, due to
higher levels of education. I performed a chi-squared analysis between SES and type of
treatment already received. The results (p=.266) lead to the conclusion that no evidence
could be found for an association between SES and type of treatment already received.
However, if the patient had already received treatment, the location treatment was
received at was shown to have a relationship with SES.
I was curious to see whether there was a relationship between SES and
respondent’s village of birth, residence, and MMC the patient attended. I did not know
whether villages in the Humla district all had similar or different SES. Varied SES
between villages could have an affect on health care seeking behavior throughout the
district. I performed a chi-squared analysis between SES and village where respondent
was born, village of residence, and village in which the patient attended the MMC. A
relationship was shown between SES and village where respondent was born, village of
residence, and village where information was collected.
Table 19: Chi-Square Test between SES and Variables
Variable Sig. df Number of cases
Decision to Bring Children or Leave them at Home .021 2 1048
Location of Treatment Previously Received .023 62 404
Village where Respondent was Born .000 122 1102
Village of Residence .000 60 1109
Village where Information was Collected .000 16 1109
Work Replacement .034 18 1097
Project II involved locating the villages of patients and MMCs which patients
attended in Humla, Nepal. Figure 5 shows a map of the most-used routes that were
traveled from patient villages to MMCs.

49
Figure 5: Walking routes from villages to MMCs (Google earth 2014)
Discussion
In this project, I attempted to identify barriers that prevented patients from
seeking health care within Humla, Nepal. The analyses I conducted helped to bring a
better understanding of socioeconomic determinants on health care seeking behavior
from six MMCs. I used the data collected from an NGO to help identify specific barriers,
and to shed light on their relative importance to health care seeking behavior among local
people. I conducted a one-way ANOVA analysis to evaluate the influence of
socioeconomic barriers on health care seeking behavior. I conducted multiple chi-squared
analyses to identify relationships between SES and health care seeking behavior. I
produced a map to help locate villages and MMCs. From GPS marked locations, I created

50
routes to help NGOs better understand the cost of travel associated with distance needed
to walk and elevation gains and losses.
This thesis tested my hypothesis that SES effects health care seeking behavior. To
test this hypothesis, I conducted a one-way ANOVA analysis, which found that SES
affected none of the variables tested. The one-way ANOVA analysis tested the effect of
SES on amount of time since treatment was last received and amount of time that was
required to travel to MMC. The one-way ANOVA analysis that tested SES and amount
of time since treatment was last received was relevant in its findings, in that, irrespective
of wealth, people were not more likely or less likely to seek health care treatment more
frequently. Since this finding seems surprising, future tests could more extensively
explore the relationship between SES and frequency of health care seeking behavior.
Reasoning for this could be explained utilizing a qualitative search for meaning and
reasoning.
The results of the one-way ANOVA analysis that tested the effect of SES on
amount of time required to travel to MMC are encouraging. These results have profound
effects on the equality of health care treatment being provided to the villagers in the
Humla district. These results mean that both rich and poor people are as likely to spend
the same amount of time traveling to an MMC. Generally, wealthier people have better
access to health care. These results indicate that, at least geographically, there is no
advantage in being wealthy and accessing health care than being poor in Humla.
Multiple chi-squared analyses determined there was a relationship between SES
and the decision to bring children or leave them at home, provision of work replacement,
location of treatment previously received, village where respondent was born, village of

51
residence, and village where information was collected. SES had an effect on the decision
to bring children or leave them at home and on work replacement. Perhaps people with a
higher SES are better able to find or hire childcare and work replacement. Perhaps one’s
SES has an effect on the strength of one’s social network and support system. Although it
is interesting to find out that there is a positive relationship between SES and the decision
to bring children or leave them at home and work replacement, further analyses need to
be conducted in order to find out why this is happening. What is the relationship between
SES and childcare and SES and work replacement? Once the relationship is better
defined, qualitative analysis can help to provide in-depth reasoning.
A positive relationship between SES and location of previous treatment received
was proven significant. This is interesting, considering a one-way ANOVA analysis
showed that amount of time since previous treatment was received and SES did not have
a relationship. This means SES does not have an effect on the frequency of treatment
received, but it does have an effect on where treatment is received.
Village where respondent was born, village of residence, and village where
information was collected were all shown to have a positive relationship with SES. This
implies that the village that people reside in has an impact on their SES. Further
exploration needs to find out explanatory reasons for this relationship. Perhaps some
villages are wealthier than others. This finding could have an impact on health care
seeking behavior. This research has helped to better understand which variables SES
affects, however, continuing research needs to be conducted in order to understand how
and why these variables are associated with SES.
Suggestions for Further Research

52
Suggestions for further research include using the route map from villages to
MMCs within Humla, Nepal to conduct spatial analyses to determine distance-related
health seeking behavior barriers, known as distance decay. Calculating the distance and
elevation gain and loss of each route to determine whether or not the combined factors
have any effect on the willingness for patients to travel to seek health care could do this.
This route map could be used against the MMC database in measuring costs of travel to
determine distance decay (the decrease in utilization with distance) (Mueller et al. 1998,
878).
Research is needed in order to address the duplication of efforts NGOs are
providing. Further research includes identifying areas in Humla, Nepal where services are
being provided, what kinds of services are being provided, and what NGO or
organization is providing those services. The goal of this research would be to combine
efforts of various NGOs to eliminate duplication of efforts and increase the efficiency of
services being offered.
Research should also be conducted in relation gender disparities in seeking health
care at MMCs in Humla district. In the results section, 758 females were identified as
seeking health care from an MMC, and only 369 males were identified as seeking health
care from an MMC. This means that 67% of patients seen at an MMC were females and
only 33% were males. Further research needs to identify the reasoning behind this
disparity. Perhaps this number is equivalent to the amount of females and males living in
the villages due to males traveling out of the region for work. Perhaps this number is
indicative of females receiving health care when they take their children to receive health

53
care. Further research should identify the reasoning for this discrepancy in order to better
provide health care to males within Humla, Nepal.
Implications for MMCs in Health Care Behavior
Access to health care is a problem for many people in rural areas and in
economically developing countries (O’Donnell 2007, 2830). Effective health care is
oftentimes not available through the state, so NGOs have taken up a large part in trying to
provide health care for this ostracized group (Sanders and McKay 2013, 109). In Humla,
Nepal, one such intervention has been applied through the use of MMCs. Although there
is much criticism surrounding MMCs and the work of NGOs in economically developing
countries and regions such as Humla, Nepal, NGOs do provide a service to people that
could not and would not be provided without these organizations.
Strategies are needed in order to raise utilization of health care in the Humla
district of Nepal. MMCs can help to reduce barriers from both the demand and supply-
side. From a demand-side, MMCs can provide reliable, reputable, and quality health care.
From a supply-side NGOs can help to inform community households and individuals
about the positive effects of both preventative and remedial health care treatments. They
can reduce the distance that patients need to travel in order to receive health care by
providing MMCs closer to rural villages. They can provide demand-side economic
incentives (O’Donnell 2007, 2831) to offset the socioeconomic cost of health care by
providing food or money incentives worth the amount of work missed. NGOs can use
MMCs in continuing to provide social impact analyses on rural patients with the goal of
furthering the utilization of health care to this group of people. “The impact on the

54
average utilization of health services should be identified and differential effects with
socioeconomic characteristics tested” (O’Donnell 2007, 2831).
This research drew upon the theoretical framework of critical medical
anthropology to study the social production of illness in order to help better understand
socioeconomic factors imbedded in health care seeking behavior. This study was
important in the continuation and dedication of social scientists to study societies and the
greater needs of those societies before introducing social changes. It drew upon the health
behavioral model in a focus specifically on the socioeconomic determinants of health
care seeking behavior.
Access to health care is influenced by cultural and historical conditions, as well as
hegemonic systems of power (Alexandrakis 2001, 75). This project helped bring
knowledge and better understanding of barriers to health care. I conducted these analyses
in hopes of influencing policy and practice relating to making health care accessible even
to the most remote-dwelling people, using the most flexible form of health care delivery
– the mobile medical camp. The framework provided by social psychology’s health
behavior model regarding perceived barriers influenced my thinking and analysis of my
findings. As perceived barriers are noted by Hyder and Morrow to be the most predictive
factor in influencing health care seeking behavior (2005, 51), this model was used in
measuring social costs of accessing health care.

