


A Delphi Study Analysis of Best Practices for Data
Quality and Management in Healthcare Information
Systems
Chapter 1: Introduction to the Study
Introduction
Problems with data quality and data management challenge healthcare systems
here and abroad as older paper and pencil record-keeping systems continue to transition
to newer electronic environments (Reader, Gillespie, & Roberts, 2014). Countless
lawsuits involving mismanagement of data and data errors have cost the U.S. healthcare
system billions of dollars, and more importantly, have resulted in numerous accidental
deaths. Moges (2014) succinctly outlined the consequences of mismanaged data in
healthcare settings when she stated that
[one] practical example is the death of a pediatric patient because of a misplaced
decimal point in the medicine prescription and the health care organization which
overpaid $ 4 million per year in claims for patients who were no longer eligible.
Similarly, an eyewear company has incurred one million dollars annually because
of lens-grinding reworks, which were caused by data errors. Although losses from
poor DQ [data quality] vary, they are measured in the billions of dollars in
addition to costs measured in lives lost, employee and customer dissatisfactions.
(p. 2)
Rau (2016) recently penned an article cautioning caregivers about patient
discharge from healthcare facilities, claiming that patient discharge was perhaps the most

dangerous period of patient care. He recounted facts surrounding a lawsuit launched by
family members of a woman who was given a highly potent drug called Methotrexate (a
cancer drug) instead of a simple diuretic called Metolazone for her diagnosis of heart
failure (Rau, 2016). The amount of Methotrexate the patient received far exceeded the
standard dosage; the diuretic that was ordered should have been administered twice per
day, but Methotrexate was administered in its place (Rau, 2016). The toxic dose of
Methotrexate led to her untimely death, which could have easily been prevented had the
entire patient discharge team subscribed to a standard protocol (Rau, 2016). From the
pharmacist, to the pharmacy technician, to the home-health nurse, the healthcare system
failed the patient (Rau, 2016).
The United States is one of the largest healthcare markets in the world. The World
Bank (2014) reported that an estimated 17% of the U.S. gross domestic product, or
approximately $2.9 trillion, was spent on healthcare in 2013. There are aspects of the U.S.
healthcare system concerning information management that are of the utmost importance,
specifically data quality issues. According to Eckerson (2002), at The Data Warehousing
Institute, countless organizations will share $600 billion a year in costs because of limited
understanding of perceived and real data quality issues. Clack and Woeppel (2018) found
that organizations that create a data-driven environment saw an increase in revenue by
6% and an increase in productivity by 5% over their industries’ competitors. To improve
quality outcomes and reduce costs, organizations may find it advantageous to include data
analytics that will utilize quality measures and best practices. Information in the form of
raw data is often referred to as the lifeblood of healthcare organizations—an essential

component of daily, data-driven, decision-making processes across multiple institutional
contexts (Foshay & Kuziemsky, 2014). The quality and integrity of healthcare data are
essential not only to the overall provision of superior healthcare but also to organizational
effectiveness in the delivery of care and services.
The management of data quality and data integrity are central to quality healthcare
(Cruz-Correia et al., 2013). As most healthcare organizations transition to electronic
health records (EHRs), data quality management has become a critical area of focus
within the healthcare industry (Jamoom, Patel, Furukawa, & King, 2014). There are
multiple challenges regarding data quality, including the possibility of inaccuracies and
data fragmentation (Adler-Milstein & Jha, 2013). The growth of information systems, the
demand for information in a real-time format, and an increased volume of raw data
gathered from healthcare systems have all led to an increased awareness of and the need
for solutions and a set of best practices for data handling (Singh & Singh, 2010). Despite
the need for solutions, there is a dearth of information about primary data problems
affecting many healthcare organizations and how they are managed.
This chapter includes the background of the study, the problem statement, purpose
statement, and research question. Also included is the conceptual framework and an
overview of the nature of the study. I conclude the chapter with the limitations,
delimitations, and scope of the study.
Background of the Study
Leaders of healthcare organizations have sought avenues for quality improvement
in a number of areas. The advent of linking the quality of care for a patient to the quality

of data captured has prompted the U.S. government to take notice and to create initiatives
for these organizations to invest in improving data quality and/or diagnose areas in their
data workflow that could be enhanced (Reiter et al., 2014). Two incentives for
improvement, the Health Technology Information for Economic and Clinical Health Act,
in conjunction with federal standards for meaningful use of EHR systems, have prompted
healthcare facilities that admitted patients (hospitals) to develop electronic surveillance
methods for reporting healthcare-associated infections (Atreja, Gordon, Pollock, Olmsted,
& Brennan, 2008; Jha, 2011). Deming (1986) recognized problems with data quality
issues in a rapidly changing healthcare system in the mid-1980s and asserted that
management was the key to improving data quality and to mitigating errors industry
wide. Improvement suggests change. In terms of change, one that has had a significant
effect, both on healthcare providers and on recipients of healthcare services, is the
treatment and management of data (Deming, 1986). With the emergence of paperless
business transactions, the healthcare industry is well into the process of transitioning from
paper and pencil data gathering and physical repositories to a new-age electronic
environment. This newer environment offers healthcare providers the opportunity to store
unlimited data offsite, enhancing security, as well as providing electronic portals for easy
document retrieval to any number of healthcare workers and patients.
Technological change is not without its challenges. The extent to which people in
the healthcare industry are adversely affected by ongoing change is highlighted in the
literature to include the topic of quality improvement. In a sample of six countries that

included the United States, the United Kingdom, and France, 91% of organizations are
trying to manage data quality errors (Experian Data Quality, 2013). Experian Data
Quality (2013) reported that the percentage of inaccurate data has risen from 17% to 22% in
less than a year. Organizational leaders in the United States believe that 25% of their data
suffers from inaccuracies that point to human error (at 59%) as the most significant factor for
data inaccuracies (Experian Data Quality, 2013). The report revealed that 66% of
organizations surveyed have not successfully developed a solid data quality management
system (Experian Data Quality, 2013).
Researchers such as Adler-Milstein and Jha (2013), Schultz (2013), Foshay and
Kuziemsky (2014), and Chen, Chiang, and Storey (2012) have tried to ameliorate
particular data quality issues with business intelligence (BI) tools in the form of big data
(a business tool used to take substantial amounts of data and analyze them for relevance
and implications). These tools are often integrated into a data warehouse for information
that could be extracted from reports for decision-making (Loshin, 2001; Singh & Singh,
2010). A few researchers have tried to mitigate data quality deficiencies with an
implementation of big data tools and to meet government requirements, such as
meaningful use criteria, in order to receive incentives (Charles, Gabriel, & Furukawa,
2014). In addition, United States government officials have created initiative programs to
encourage healthcare organizations that would implement EHR systems (Charles,
Gabriel, & Furukawa, 2014). Accreditation programs and organizations such as Centers
for Medicare & Medicaid Services seek to offer standardized, quality measures that hold
healthcare organizations accountable for the quality of their data and patient care

(Charles, Gabriel, & Furukawa, 2014). There is an oversight by those who encourage
healthcare leaders to engage in organizational self-assessment and ongoing research to
implement best practices for data quality and management. According to Holzinger,
Dehmer, and Jurisica (2014), research is needed on frameworks that identify exceptions
in data quality to address the process managed by humans and computers used to
manipulate data. Duggirala et al. (2016) posited that information mining of different
sources, such as medical writing, EHRs, and online networking, share a significant
number of the difficulties identified with security reports information. The nature of
information in these sources can be more reliable, contingent upon the structure of the
database and the preparation of the individuals who enter the information, shifting from
apparently high caliber to a lower grade of information (Duggirala et al., 2016). Logical
difficulties will continue to grow with the expansion of new reconnaissance information
sources and the advancement of new techniques for submitting unconstrained reports
from online and versatile applications (Duggirala et al., 2016). It will be critical for
organizations with huge datasets such as the Food and Drug Administration to structure
its data innovation frameworks with the goal that information can be submitted,
recovered, prepared, and assessed in an institutionalized way. These incorporate EHRs,
personal health, claims, models for health information, information from government and
private cell phones for following health plans, and information from social sites such as
websites, quiet backing bunch locales, and inquiry term logs (Duggirala et al., 2016).
Much of the research on data quality has become the mission of independent, private, and
government organizations such as the Healthcare Information and Management Systems

Society (HIMSS), Experian, National Institutes of Health, American Society for Quality,
Agency for Healthcare Research and Quality, American Health Information Management
Association, and Gartner. The research from these organizations has demonstrated that
these information sources can be of an incentive in postshowcase healthcare observation
and other related fields. Facilitating improvement and usage of a progressed and
coordinated secure information mining framework upheld by suitably experienced work
force will be fundamental for better educated basic leadership and healthcare
administration to continuously monitor for issues (Duggirala et al., 2016; Holzinger et al.,
2014). Empirical research is needed to keep the industry aware of current data
management practices within healthcare organizations as well as the success rates of an
organization’s adopted data management practice. In this research, I employed
contemporary guidelines and ideas for organizations seeking to implement best practice
data management, such as assessment of data quality and data management needs. These
helped to ensure that effective decision-making techniques are being applied as
technology-driven healthcare modes continue to evolve.
The search for innovative ways to manage the growing amount of data has created
opportunities for the introduction of new technology. The introduction of EHRs has
allowed healthcare centers access to vast amounts of data, as well as patient access to
records through the use of patient portals. As a result, healthcare organizations have made
changes to their work practices and processes for using data acquired from EHRs (Tolar
& Balka, 2012). At question is whether data quality issues and data integrity of

information retrieved from EHRs are being identified and how those data are being
managed.
Problem Statement
Data quality and data integrity concerns such as a lack of shared patient history
between health care providers, improper coding, insufficient enrollment or insurance
information, which has led to the denial of referrals, or data inconsistencies, are not being
addressed as often as necessary, all of which adversely affect the delivery of quality care.
Multiple challenges pertain to data quality and integrity, including inaccuracies and data
fragmentation (Adler-Milstein & Jha, 2013). The general problem is that patients and
healthcare organizations are adversely affected by poor data quality (Anderka et al.,
2015). Data quality involves the accuracy and completeness of collecting data,
consistency of processing the data, and timeliness of data usage (Dixon, Siegel, Oemig &
Grannis, 2013).
Errors in demographic information could, and sometimes do, adversely affect key
management decisions. This and other aspects of inaccurate data quality for patients and
healthcare organizations have been found to be a consequence of using data acquired and
processed for later use, resulting in diminished healthcare service to the community
(Mawilmada, Smith, & Sahama, 2012). Mawilmada, Smith, & Sahama (2012) expressed
that secondary data received from out of an EHR are used primarily for reporting
purposes. Reported data cannot be considered usable if the data are bad. According to one
Oracle report (2015), as much as $70.2 million in annual revenue is not sustainable when
accurate secondary data are not available for sound decision-making (p. 29). Another

study completed by Information Builders (2013) identified that nearly 15% to 20% of
annual revenue from the influx of new and current patients is lost due to inaccurate
secondary data (p. 3).
The specific problem is that healthcare leaders need a better understanding of how
best practices can be used to effectively manage accurate patient information (Rau, 2016).
Bowman (2013) and Weiskopf and Weng (2013) reported that processes and protocols to
mitigate data quality errors and to identify their causes or even obtain viable information
on EHR data quality and integrity remain scarce in the literature.
Purpose of the Study
The purpose of this qualitative Delphi study was to identify best practices for data
quality and data management in healthcare systems. This study has the potential to inform
leaders on the implementation of best practice guidelines for data quality and data
management.
Nature of the Study
The research method most appropriate for this study was qualitative. According to
Baxter and Jack (2008), a qualitative approach allows users and managers of
organizational systems an opportunity and provides information based upon their
interpretations of ongoing processes activities and data. The research method allowed for
virtual interactions between smaller nonrandomly selected participants and their
responses to be studied as a whole and for patterns and themes to be identified, where a
quantitative study would not. This study consisted of three rounds of questions for a panel
of IT and non-IT healthcare data experts who met the selection criteria identified in

Chapter 3. The multiperspective survey population consisted of 25 different healthcare
systems data management professionals across the United States who have worked or are
working for a healthcare system such as an EHR and have managed the data within this
system. From that population, 25 participants were selected using purposive sampling to
secure critical perspectives from participants. Twenty participants were necessary to
provide a more robust outlook on the topic. An additional five participants created a
cushion in case some participants withdrew before the study was completed. With a
quantitative method, a study of data handling practices among selected participants would
have to be conducted in a controlled environment as an experimental comparison may
need to take place, whereas with a qualitative method, participants could be queried in a
more natural, comfortable environment.
The research design was a three-round Delphi study that focused on current data
quality issues and best practice ideas among healthcare systems experts. Surveys were
appropriate for the study, given they provided a focused method for acquiring pertinent
information from the selected participants (see A. von der Gracht, & Darkow, 2013;
Baxter & Jack, 2008; Jansen, 2010).
Research protocols for this study included a structured open-ended questionnaire
in the first round, followed by two rounds of a structured mix of dichotomous, Likert, and
scaling questions. A. von der Gracht and Darkow (2013) implied that the results from the
first round drive the questions for the second round. After analyzing the results from the
first round, the second round of questions were created. The third round of questions were
similarly generated. The process of data collection and healthcare data management best

practices was the focus of the data quality evaluation. In this evaluation, I specifically
sought to determine if data process errors are consistent among participants.
The two other research designs considered but not used were ethnography and
phenomenology. Ethnography would not have been appropriate as a research design for
this study, as it would have focused more on organizational culture such as rituals and
customs of the population rather than the topic. It would also have required the me to
become immersed in the organizational culture of selected research sites rather than to
observe participants from outside. Phenomenology would not have been appropriate
because it focuses on the meaning of a specific lived experience to a researched group
(see Donalek, 2004).
Definitions
The following definitions operationally defined terms that were used in this study:
Data integrity: “The extent to which healthcare data are complete, accurate,
consistent, and timely” (Data Integrity, 2017).
Data quality: “The reliability and effectiveness of data for its intended uses in
operations, decision making, and planning” (Data Quality, 2017).
Data quality assessment framework (DQAF): Framework that uses data quality
dimensions to create measurements for improvement (Sebastian-Coleman, 2012).
Data steward: An individual put in place for business purposes to track, manage,
and escalate data quality issues where they arise (Judah & Friedman, 2014).
Electronic health record (EHR): Electronic wallet of health information on a
patient that can be used in many different organizations to communicate health status, lab

results, and medications. An electronic record used to keep everyone involved in the care
of all patients equally aware (Electronic Health RecordEHR, 2017).
Health information manager: Health professional who strives to ensure the quality
of clinical data for decision-making purposes (Health Information Management, 2017).
Healthcare Information and Management Systems Society (HIMSS): Private
organization that creates educational services built on improving healthcare information
technology (HIMSS, 2015).
Conceptual Framework
Conceptual approaches were applied to guide the evaluation process in assessing
data handling practices. The conceptual framework was the data quality assessment
framework (DQAF) as the overarching guide for assessment. Figure 1 demonstrates the
concepts that ground this study. Chapter 2 addresses this framework in more detail. The
DQAF includes elements from information theory, such as the data quality dimension
concepts. Information theory was employed to evaluate the extent to which the target
panel members selected for this study have developed and used a set of best practices for
managing data quality.
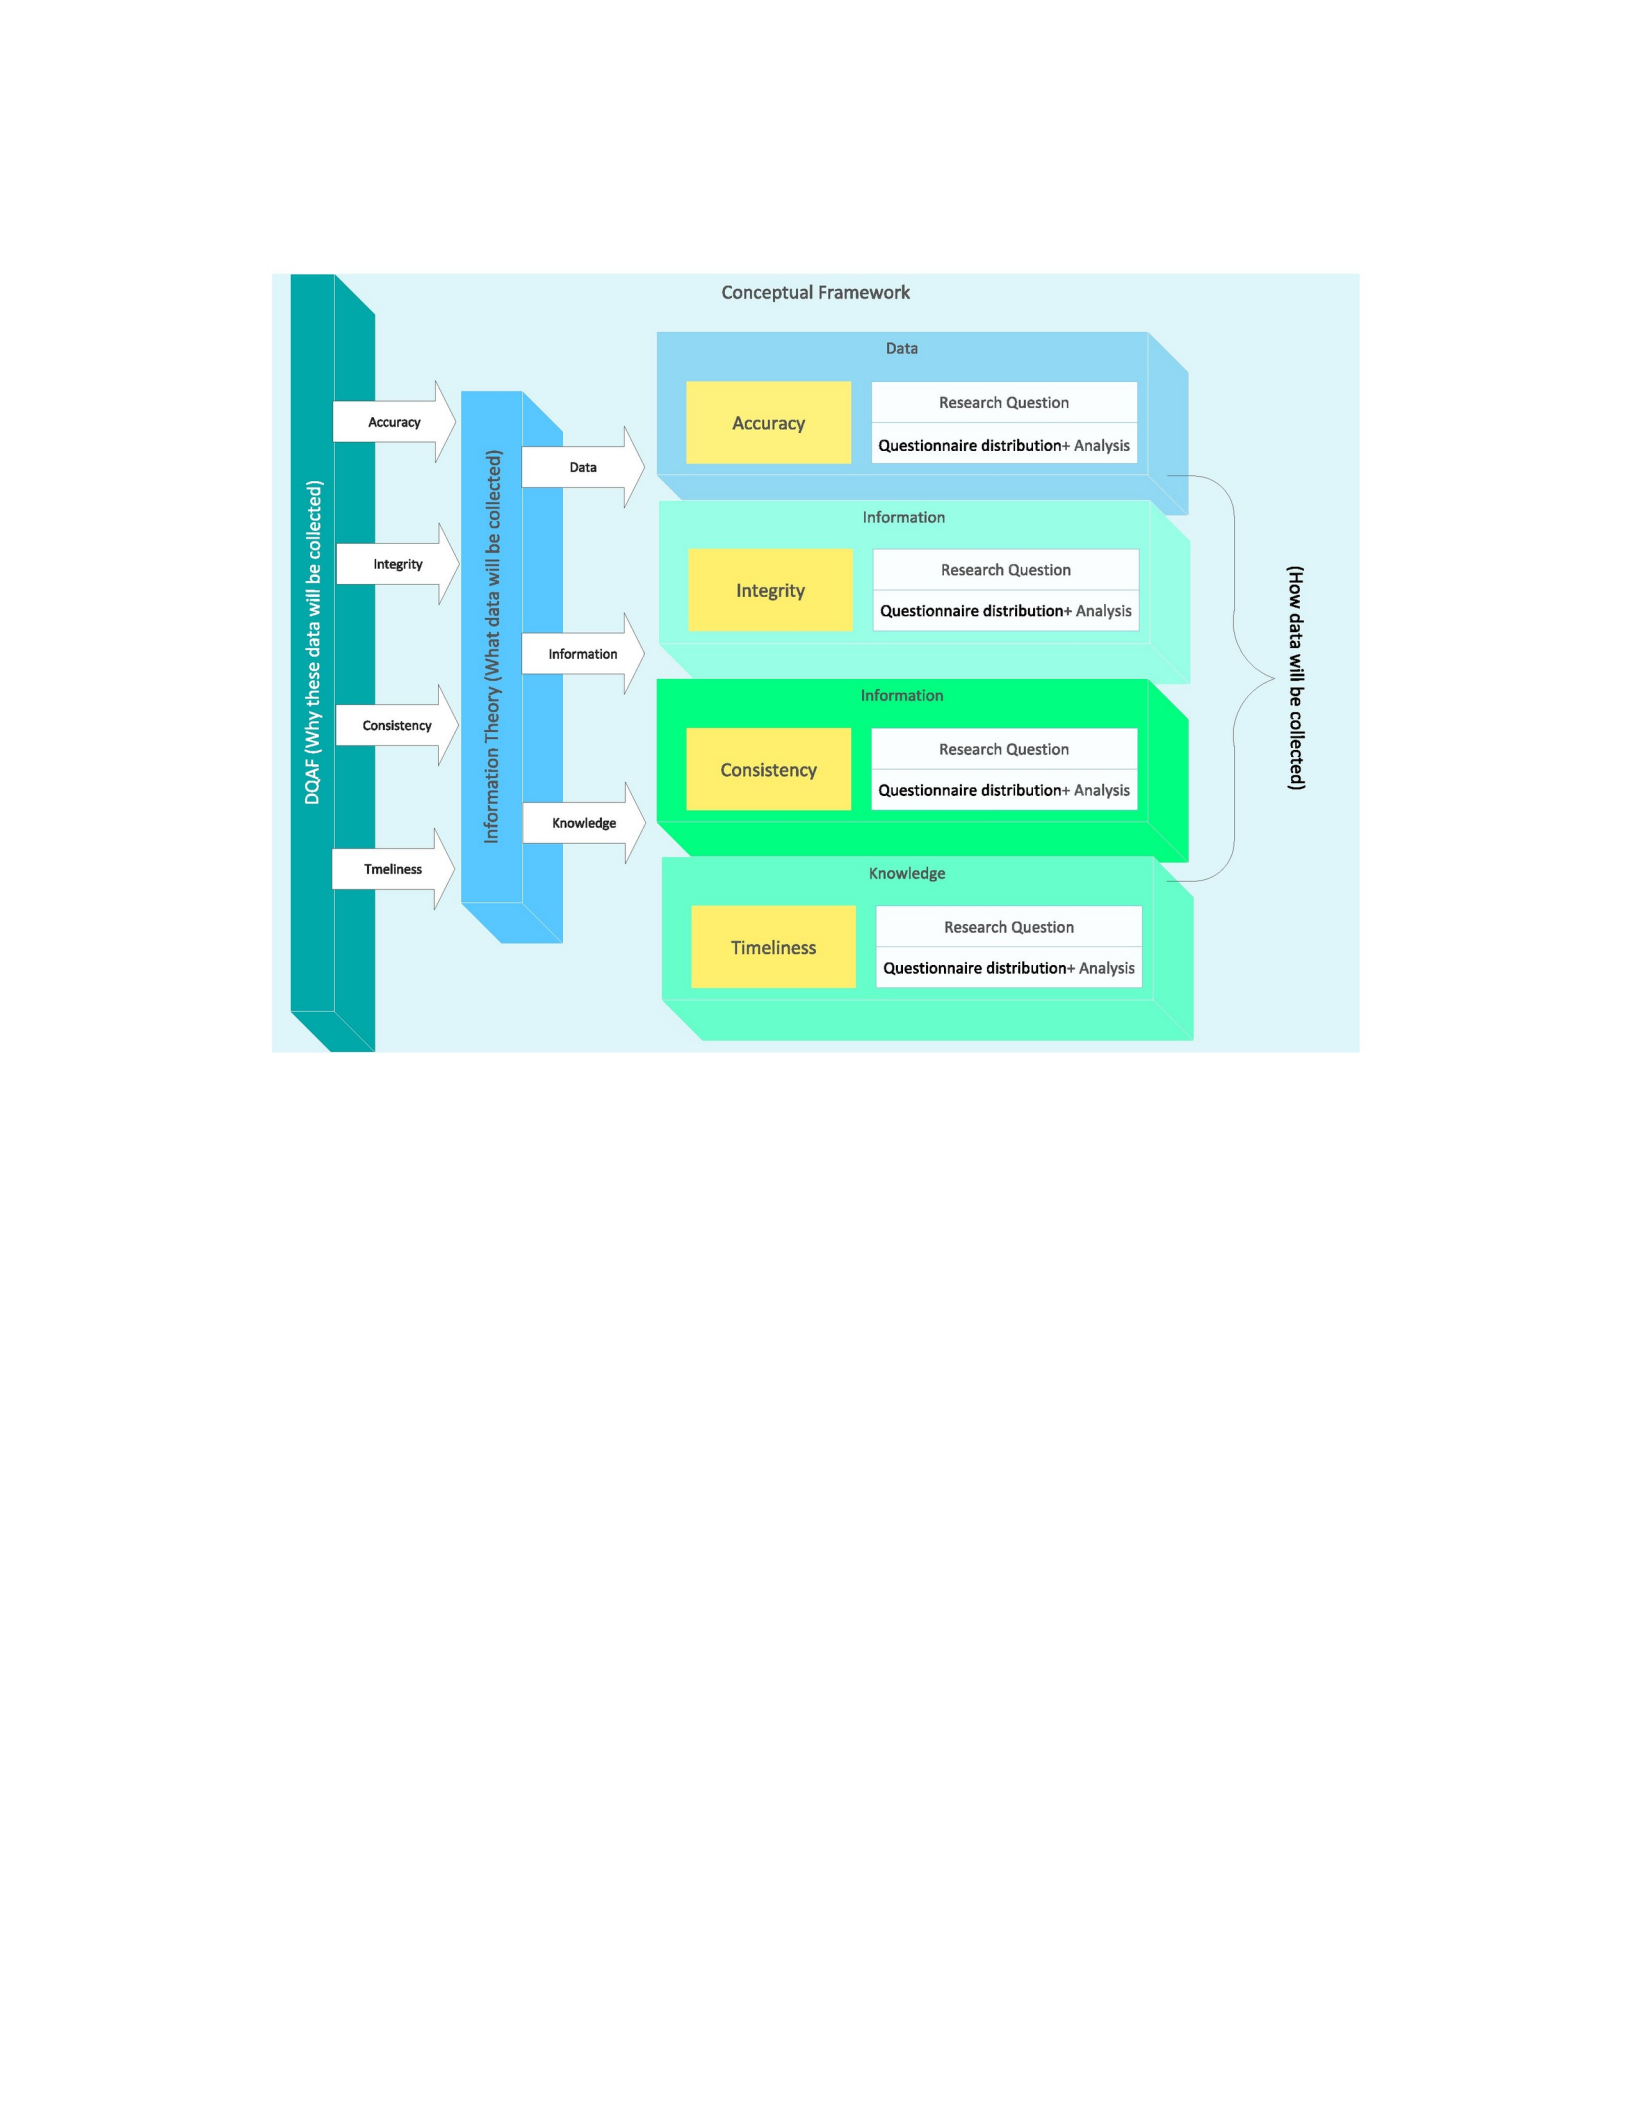
Figure 1. Conceptual framework of four categories for organizing and analyzing
data quality. Adapted from DQAF developed in 2003 by the IMF. Adapted from
“Data quality assessment framework and data quality program” by IMF, 2003,
http://www.imf.org/external/np/sta/dsbb/2003/eng/dqaf.htm. Copyright 2003 by the
International Monetary Fund.
Data Quality Assessment Framework
Originally constructed in 2003 as a qualitative solution to data quality by the
International Monetary Fund (IMF), researchers applying the DQAF use specific data
quality dimensions such as accuracy and integrity for evaluating statistical data from

countries around the world (Data quality assessment framework and data quality
program, 2003). Sebastian-Coleman (2012 asserted that the DQAF does not use accuracy
as a dimension for measurement. Instead, DQAF creators have selected validity as a more
fitting measurement, owing to their perspective that accuracy would require real world
comparisons of data in order to confirm the framework’s legitimacy.
I used the DQAF to obtain a perspective of what could be effectively used as a
standard guideline for managing data quality. I analyzed the responses of participants to
determine Round 2 and Round 3 questions. This analysis was based upon information
obtained from the healthcare IT management panel. I distinguished among three practices
by noting which type is being used by each panelist: in-house, revised, or derivative, as
modified from an accreditation agency or organization. For this study, only certain
components were necessary to create the measurements to test. The DQAF model
demonstrated the why of the data that were collected and the data quality dimensions.
Information theory provided the what of the data collected and addressed the data as data
(panel response acquisition), information (panel response), or knowledge (panel response
analysis). In a 2010 working paper, Mrkaic used information theory to further categorize
the DQAF concepts. Figure 1 shows how the DQAF was used as the overarching
framework from which measurements were created to assess the research questions and
the data collection method.
Information Theory
Information theory was originally applied as a quantitative mathematic theory.

Since its introduction, this theory has been modified and now branches into qualitative
studies and social science. Health informatics, in particular, has used this theory in a
number of studies that have launched more than a few different models, to include the
Blum model (Nelson & Staggers, 2014). In this study, I applied the Blum model. The
model falls under the umbrella of information theory and is one of the most widely used
models within health informatics. It can be used to address the processing of data as three
elements: data, information, and knowledge. This model uses the processing of elements
to explain the creation of descriptive categories and their relationships to each other. This
model was employed in the study through surveys in order to disclose how users enter
data, mange the data, and translate to information for managers to apply.
Merging the Two Theories
As patient data are entered into an EHR, a margin for error exists—incorrect dates
of service, omissions of one or more medications, incorrect measures of laboratory
reports, as well as the addition to a patient’s record of surgeries or conditions that were in
error yet continued to be carried forward as part of the digital record, to name a few. End
users of entered data make treatment decisions based upon information contained in an
EHR, often without clarification from the patient regarding the authenticity of their EHR.
As a result, the accurate processing of patient records continues to plague the healthcare
industry. Literature findings on information theory and the DQAF support the above
claim of conflicts in the accurate processing of data (Panahy et al., 2013). Mishaps have
been found to occur at the acquisition (data input) stage due to an inadequate
understanding of how data will be used in the final output or at the final stage when faulty

communication occurs on what output is expected (Panahy et al., 2013). Data quality
dimensions found in the DQAF can be used to find areas of improvement in the process
of a system and its information (Panahy et al., 2013).
Research Question
This study was guided by one essential question:
Research Question: What practices contribute to identifying improvements in
EHR data collection, secondary use of data, data quality, and integrity?
Assumptions
The research was based on four assumptions. The first assumption was that all the
participants’ responses were honest, detailed, and straightforward. I assumed that all
selected participants would fully participate in all three rounds. I also assumed that the IT
managers who were chosen to participate were aware of and actively monitoring data
quality or have performed this duty in their past experience. Another assumption was that
they had the same level of experience; however, each participant could have their own
unique experience with the topic or the field of study.
Scope and Delimitations
The purpose of the study was to investigate best practices for electronic data
management through the perspectives and experience of the participants. I sent out
surveys to healthcare IT managers. The specific systems managers who were used for this
study were those identified as data stewards. Each data steward was selected based on
that employee’s role as liaison through multiple departments, executing multiple
activities, and on that employee’s ownership of the data. According to a Mass Storage

Systems and Technologies report submitted by Duerr, Parsons, Marquis, Dichtl, &
Mullins (2004), the position of data steward has been in service for more than a decade
with the creation of World Data Centers in 1957-1958, but it is newly recognized as a
critical position for managing data (p. 48). IT managers with the titles of database
administrator, database architect, and data analyst were also considered, as their roles in
the organization largely address such design and other technical issues as security,
performance, and database backup, while the data steward is responsible for addressing
policies, procedures, and data standards (see Loshin, 2001).
Panahy et al. (2013) indicated that managers depend on the quality of data to
make useful decisions. Other healthcare management positions such as directors and vice
presidents were also considered but not selected, as they represent higher level
management positions where decisions do not affect organizational data that directly
impact the community.
The United States was selected as the geographical location to study because it
represents the third largest populated country in the world from which to gather
substantial healthcare information (see Harder, 2013). In addition, it is highly diverse,
with an estimated population of 325,719,178 as of July 1, 2017 from which to draw
participants (see U.S. Census Bureau, 2017). Smaller more focused pools of participants
from metropolitan cities like New York, Philadelphia, or Chicago with large culturally
diverse populations were also considered but not selected. Population figures across the
United States are much greater.

The selection of the United States with its many IT healthcare managers
constituted a delimitation of the study. This geographic location was selected in order to
avoid the potential for an enormous population of participants, such as that from the
addition of other countries. A larger geographic location—other countries—limits the
researcher’s ability to be flexible with participants’ schedules and time zone. Another
delimitation was the inclusion of only IT managers that manage the data collected.
Although expanding the study to include other healthcare systems and data users was
considered, the inclusion could well return much irrelevant information.
Limitations
The potential limitations of this study involved time, sample, questions, authentic
response, and suggestions. Time constraints and conditions for participants were a cause
for concern. The study took place over a 4-month period. Within this time, some
participants were not able to dedicate the required time to complete the survey for each
round. This limitation was addressed by providing more than one option for survey
submit date, system scheduling for surveys, and predeterminations of the process for
analysis of the collected responses.
Heterogeneous purposive sampling could produce a sense of bias during
participant selection process. I applied maximum variation purposive sampling to secure
critical perspectives from participants (see Palinkas et al., 2015). I used a list of
participants with a specific expertise identified in Chapter 3.
Some questions may have been difficult for participants to understand, which
might have resulted in skewed responses. To lessen the chances of a question being too

difficult to answer or the response being skewed, I phrased the questions using industry
standard terminology and provided a space for additional information. A field test of the
Round 1 questions was conducted using three experts in the field to refine the questions.
Significance of the Study
This study has the potential to address the gap in literature regarding the lack of
empirical studies on best practices to mitigate data quality concerns in healthcare EHR
systems. The study’s findings could prove significant to the healthcare industry, the
public, and practitioners by corroborating prior findings of relevance and by disclosing
the need for further research. Moreover, these findings may be significant to the
healthcare industry, the public, and practitioners, as they have the potential to provide
further evidence of previously reported issues and new problems that may not be reflected
in other studies. Accurate data quality measures could strengthen the decisionmaking
process for healthcare services and quality of patient care.
New findings may also extend the knowledge base and usher in newer protocols
for data handling. Some researchers (Adler-Milstein & Jha, 2013; Chen et al., 2012;
Foshay & Kuziemsky, 2014; Schultz, 2013) have tried to ameliorate particular data
quality issues with BI tools in the form of big data (a business tool used to analyze large
amounts of data for relevance and implications). A few researchers have tried to mitigate
data quality issues with an EHR implementation to meet government requirements in
order to receive incentives (Charles, Gabriel, & Furukawa, 2014).

This research can aid in the development of best practice guidelines and
accountability measures to reduce the number of digital errors EHRs to implement and
manage data for optimal results and quality assurance.
Significance to Management and Technology
This study will contribute to the knowledge base for the management of data
quality in producing information that is readily applicable. With an increasing number of
healthcare organizations implementing EHR systems for data management, the need for
error-free data will continue to grow. The health industry could benefit from this study by
using the data to launch more studies on data quality and data management obstacles. The
healthcare industry could be able to manage their data more efficiently by critically
identifying, assessing, and implementing some or all identified best practices as a
solution.
Significance to Theory
This study could provide useful secondary data for efficient decisions and assist in
providing the best delivery of care for healthcare organizations and may eventually lead
to new theory development. The process to develop this theory would begin with
observing current data workflow practices that are identified in the EHR system and the
management related to the acquired data. The next step would be to evaluate new data
quality errors discovered as a result of this research project and to develop methods of
ameliorating them. The last step would be to identify better guidelines for data error
prevention that can be consistently applied based upon the most identified data errors or

mistakes revealed in the study, and the best practices for quality and error-free data within
healthcare organizations.
Significance to Social Change
This study has the potential to be significant, as it may offer insights that could
affect the way healthcare organizational leaders and managers view their data and make
decisions within their communities based upon said data. Trends and patterns identified in
the study could also provide a basis for understanding what data quality deficiencies may
be present in the secondary data when making determinations about services. Such trends
and patterns could eventually strengthen patient quality of care. The public could benefit
from this study’s findings, as there could be an increase in needed services in the
community. The findings could ameliorate healthcare service reductions or even
eliminations that result from insufficient or incorrect data.
Summary and Transition
Chapter 1 addressed the problem of adverse effects within healthcare due to
inadequate or questionable quality of data used to make decisions on healthcare delivery.
The study could illuminate best practices in healthcare and could meaningfully connect
findings to the academic fields of management and technology. The conceptual
framework of Blum and DQAF were used to guide the structure of Delphi survey
questions and to identify what information to collect. The DQAF provided assessment
measures based upon data quality dimensions, and information theory (Blum model)
helped to categorize the type of information that fell into each data quality dimension
assessed. Chapter 2 is a literature review on the main themes of quality management as it

has evolved into data quality management. In Chapter 3, I detail the study’s methodology
and design. In Chapter 4, I display research data collections and findings. Chapter 5
contains my analysis of the study’s findings and linkages to needed future research.
Chapter 2: Literature Review
Introduction
Data workflow practices for identifying data quality and managing data quality
deficiencies have yet to be standardized to ensure optimal delivery of care and services to
patients. The reasons for poor data quality range from human error to insufficient data,
with human error as the leading cause of poor data quality. Moreover, Bowman (2013)
suggested human error or user error as one of the leading causes of data quality issues
within an EHR. According to a study by the HIMSS (2014), poor data quality becomes
evident in healthcare organizations when errors and insufficiencies appear in the process
and delivery of care as well as a decline in appropriate decision-making as a result of
unreliable data. There are multiple challenges concerning data quality and integrity,
including inaccuracies and data fragmentation (Adler-Milstein & Jha, 2013).
Bowman (2013) and Weiskopf and Weng (2013) reported that they found little
information regarding poor EHR data quality and integrity. From the available research,
Bowman and Weiskopf and Weng concluded that nobody has addressed a strategy to
mitigate data quality errors, such as incorrect information found on lab reports, patient
enrollment forms, or imported patient records. Another strategy identifying causes of data
quality errors is attributed to data input quality such as lack of communication and
crosscheck (Bowman. 2013). Human error is attributed to potential for data errors,

ranging from data input practices of clerks to data users in management positions
(Weiskopf and Weng, 2013). As most healthcare organizations transition to EHRs, data
quality management has become a critical area of focus within healthcare organizations
(Jamoom et al., 2014). The purpose of this qualitative Delphi study was to identify best
practices for data quality and data management in healthcare systems. As the literature
has indicated, the healthcare industry lacks a systematic approach to resolving human
errors in electronic data handling. Some of these errors have led to untimely deaths,
incorrect diagnoses, loss of revenue for healthcare organizations, and other failures that
have contributed to substandard health care. The results of this study could assist in the
development of a set of guidelines for quality control of data handling practices within
U.S. healthcare systems.
While a number of research articles have addressed multiple problems concerning
data quality within healthcare organizations in general, few researchers have examined
the nature of data quality and related data management practices. Poor data quality within
EHRs results in lost reimbursements and reduced patient safety as well as a loss of
services to communities and increased operating costs (Brown, Weber, & DeBie, 2014;
Foot et al., 2014; Todoran, Lecornu, Khenchaf, & Caillec, 2015). The purpose of this
literature review was to align information obtained from articles and theories with current
data management practices in healthcare systems today and to contribute research
findings as a first step in the identification of universal or common practices of healthcare
data handlers and users. With the identification of universal or common practices, my
next step was to create a systematic approach for identifying and managing data quality
issues as a path to the development of a set of data quality best practices. The review in
this chapter reveals the need for the study by disclosing the lack of empirical studies
available on this topic.
Chapter 2 addresses available literature on the following topics: (a) relevant
theories in quality management, (b) trends in applying general quality management
theories to assess and improve data quality, (c) healthcare organizations’ current data
quality concerns, and (d) common practices to address data errors and data quality
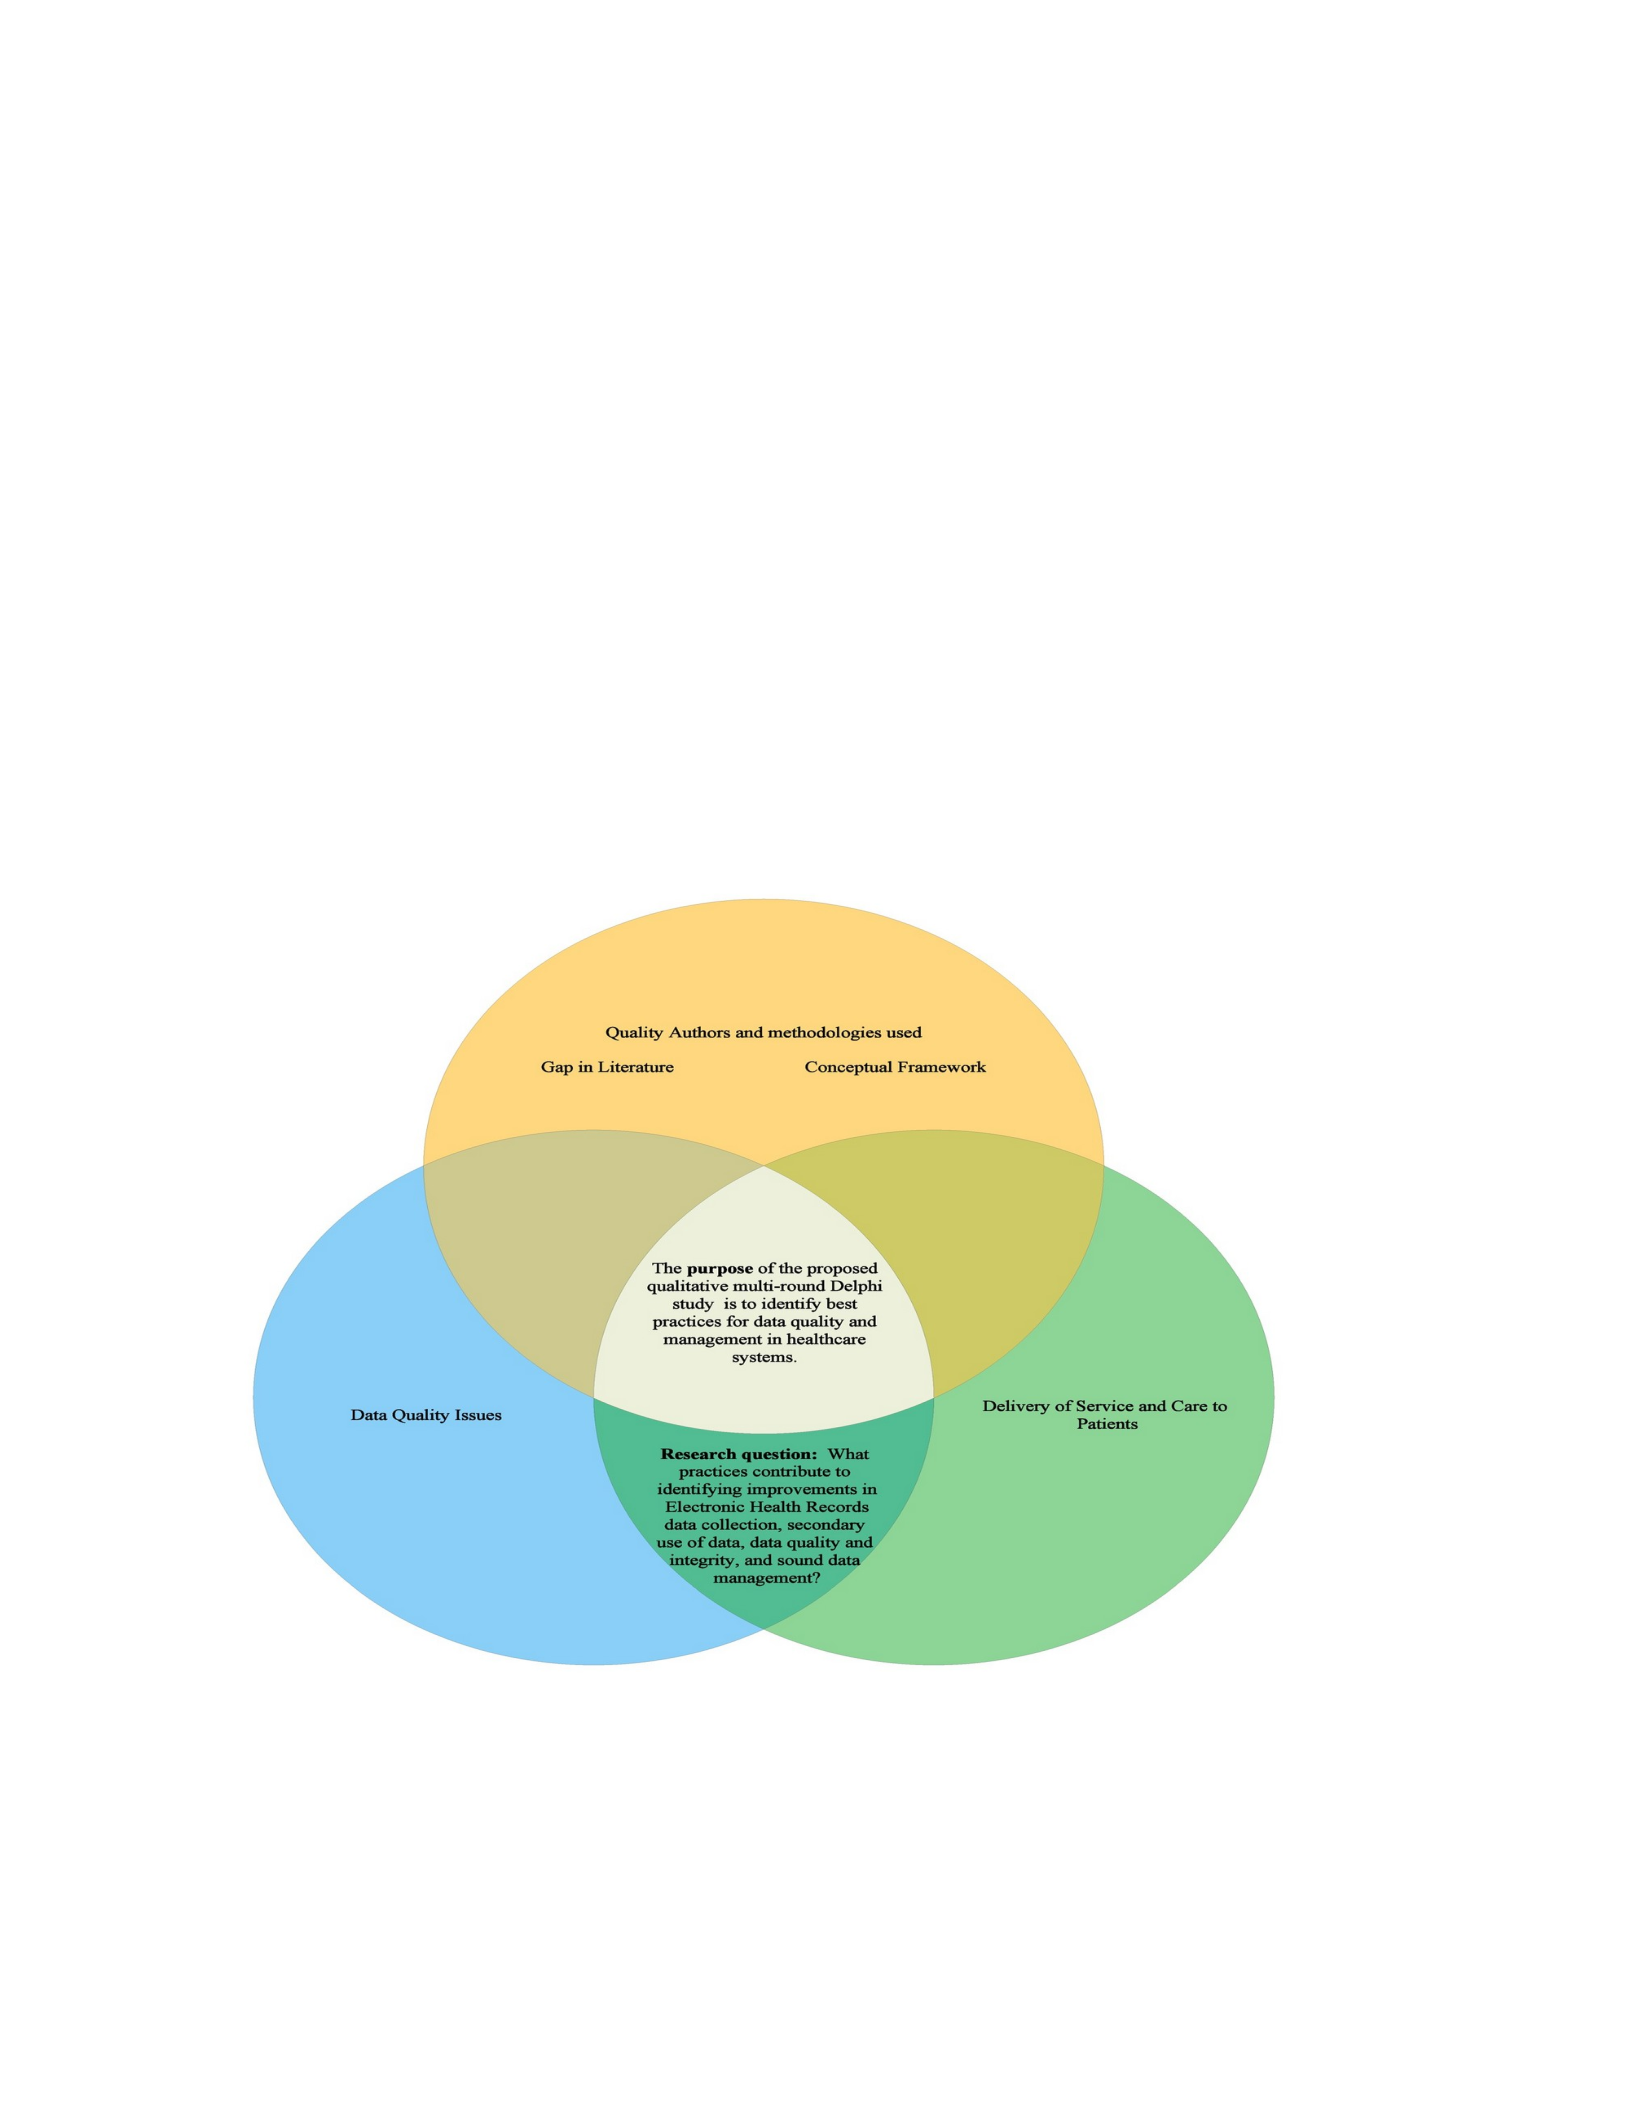
management. The diagram in Figure 2 depicts the linkage of themes, research question,
and purpose of the study.
Figure 2. Literature review linkages.

The review of literature supports the research question, selected methodologies,
and design of the study. Chapter 2 consist of these major sections: (a) Introduction, (b)
Literature Search Strategy, (c) Conceptual Framework, (d) Seminal Authors in Data
Quality Management, (e) Gap in Literature, (f) Data Quality issues, (g) Delivery of
Service and Care to Patients, and (h) Summary.
Literature Search Strategy
The following search terms and keywords were used to search scholarly
databases and were deemed optimal to acquire information specific to data quality and the
healthcare industry: data quality dimension, data quality, data integrity, electronic health
record, data completeness, data timeliness, data consistency, data accuracy, data quality
assessment framework, open systems theory, information theory, Blum model, health
informatics, data quality issues, data quality problems, poor data quality, data quality
characteristics, history of data quality, data quality in healthcare, impact of bad data,
bad data, data in healthcare, theories used in healthcare, data quality in EHRs, case
studies in healthcare, methodologies and designs used in healthcare, qualitative studies,
and delphi method.
Database searches included the following categories: general databases, technical
databases, and health sciences databases. The specific names of these databases included
Proquest Dissertations & Theses, Dissertations & Theses at Walden University, ebrary,
EBSCO eBooks, Google Scholar, JSTOR, SAGE Encyclopedias, SAGE, Premier, SAGE
Research Methods Online, IEEE Xplore Digital Library, Safari Tech Books, Science
Journals, MEDLINE with Full Text, CINAHL Plus with Full Text, ProQuest Nursing &
Allied Health Source, Health & Medical Complete, CINAHL & MEDLINE
Simultaneous Search, PubMed, Science Direct, and Cochrane Database of Systematic
Reviews. The New York City library was also used to acquire older books in order to
place the topic within its historical context and to complete historical information for
other databases. Table 1 displays the sources searched, material found, and material used.
Table 1
Literature Search Sources
Source Peer
reviewed
articles
found
Peer
reviewed
articles
used
Books
searched
Books
used
Dissertations
searched
Dissertations
used
General
databases
5, 680 80 20 2 50 3
Technical
databases
2, 584 75 10 4 0 0
Health
sciences
databases
8,393 50 10 2 0 0
Library 80 20 30 5 0 0
Total 8,473 225 70 13 50 3
Conceptual Framework
There was one conceptual framework applied to this study: the DQAF. This
framework was originally created to improve data quality through measurements and data
quality dimensions within systems in the economic sector but was later modified and used
in other sectors such as education (Sebastian-Coleman, 2012). The DQAF helped to drive
the assessment of the data that were collected to support this study. The most frequently
used data quality dimensions were also used to steer the collection of the data.

The DQAF allows for the acknowledgement of the assumptions of data quality,
data integrity, and data management processes to be addressed by staff who collect the
data. In this scenario, measurements were created as a product of the information
acquired by data collected from panelists regarding data within EHRs and possible
decisions made and manage the actual data. DQAF addressed both the data collection and
data management aspect of the study. Senkubuge, Modisenyane, and Bishaw (2014) used
the DQAF as a framework within their methodology to assess the connections between
health sector reform processes and reinforcement of health systems. Senkubuge et al.
found that there was a lack of government participation in strengthening healthcare
systems. They also asserted that there is a need to prioritize between different
stakeholders as to what policies should be put in place as well as who will own and
manage these systems (Senkubuge et al., 2014).
These findings demonstrate a need for stakeholder contribution and commitment
to create a well-managed system. The researchers also addressed availability and
accuracy of data problems as well as the absence of sufficiently trained employees in
healthcare systems worldwide (Senkubuge et al., 2014). Jerven (2014) determined that
errors due to omissions created an accuracy problem with statistical data and indicated
that omissions resulted in unreliable data. Jerven used the DQAF, evaluating six fields
with five data quality and summarizing dimensions of 16 reports from the IMF on the
African trade economy. Three of the five data quality dimensions used in Jerven’s study
were used in my study: serviceability (timeliness), accuracy, and integrity

(completeness). Accuracy relates to information theory (Blum model), which uses the
approach of processing data, knowledge, and information (Blum, 1986).
Nelson and Staggers (2014) reported, that since its introduction in the mid-1950s,
information theory has been modified from its quantitative origins to now include
qualitative studies and social science. The catalyst for information theory was the
invention of the computer. Adherents of information theory attempt to link the process of
knowledge acquisition in the human brain to computer operations from data input to
output. Health informatics, in particular, has used this theory in countless studies,
launching a number of different models such as the Blum model (Holzinger et al., 2014;
Nelson & Staggers, 2014). Scott, Sera, and Georgopoulos (2015) explained their use of
information theory relative to quantitative evaluations of how decisions are made over
knowledge domains. The study consisted of 16 different tasks and questioned what tasks
were repeated most often and how they should be categorized (Scott et al., 2015). Scott et
al. found that by using a version of information theory (entropy), participants acquired a
better understanding of the importance of education.
Todoran, Lecornu, Khenchaf & Caillec (2015) concluded that information theory
was the most appropriate theory to use when assessing information quality. They reported
that the theory yielded a lens through which to view outcomes used for decision making.
The findings from their study a connection provided a justification for my use of
information theory in that it informed my study in categorizing results for information
quality.

The Blum model falls under the umbrella of information theory and is one of the
most widely used models within health informatics to address the processing of data
focusing on three elements: data, information, and knowledge. This model uses the
processing of elements to explain the building and linkage of elements to render a final
product much like the design of a flow chart depicting the steps involved with playing
sports. This model was fundamental to my study to show how the data received is
digitally entered by users to create information and for managers to use as knowledge in
decision making. Within this process, there is a breakdown that occurs with the quality of
data entered into the electronic record keeping system. This breakdown could occur at the
data acquisition level due to the lack of understanding of how the data will be used in the
final output, or there could be a breakdown in communication on what final output is
expected.
Figure 3 shows the assessment breakdown of how the data quality assessment
framework and information theory can be used to evaluate collected data. The assessment
of the internal and external validity of the data input by personnel who engage in digital
record entry and management are the focus of data quality during this research.
Information theory will specifically address the data collection aspect of this study by
applying consistency, integrity, accuracy, and timeliness to data, knowledge, and
information.
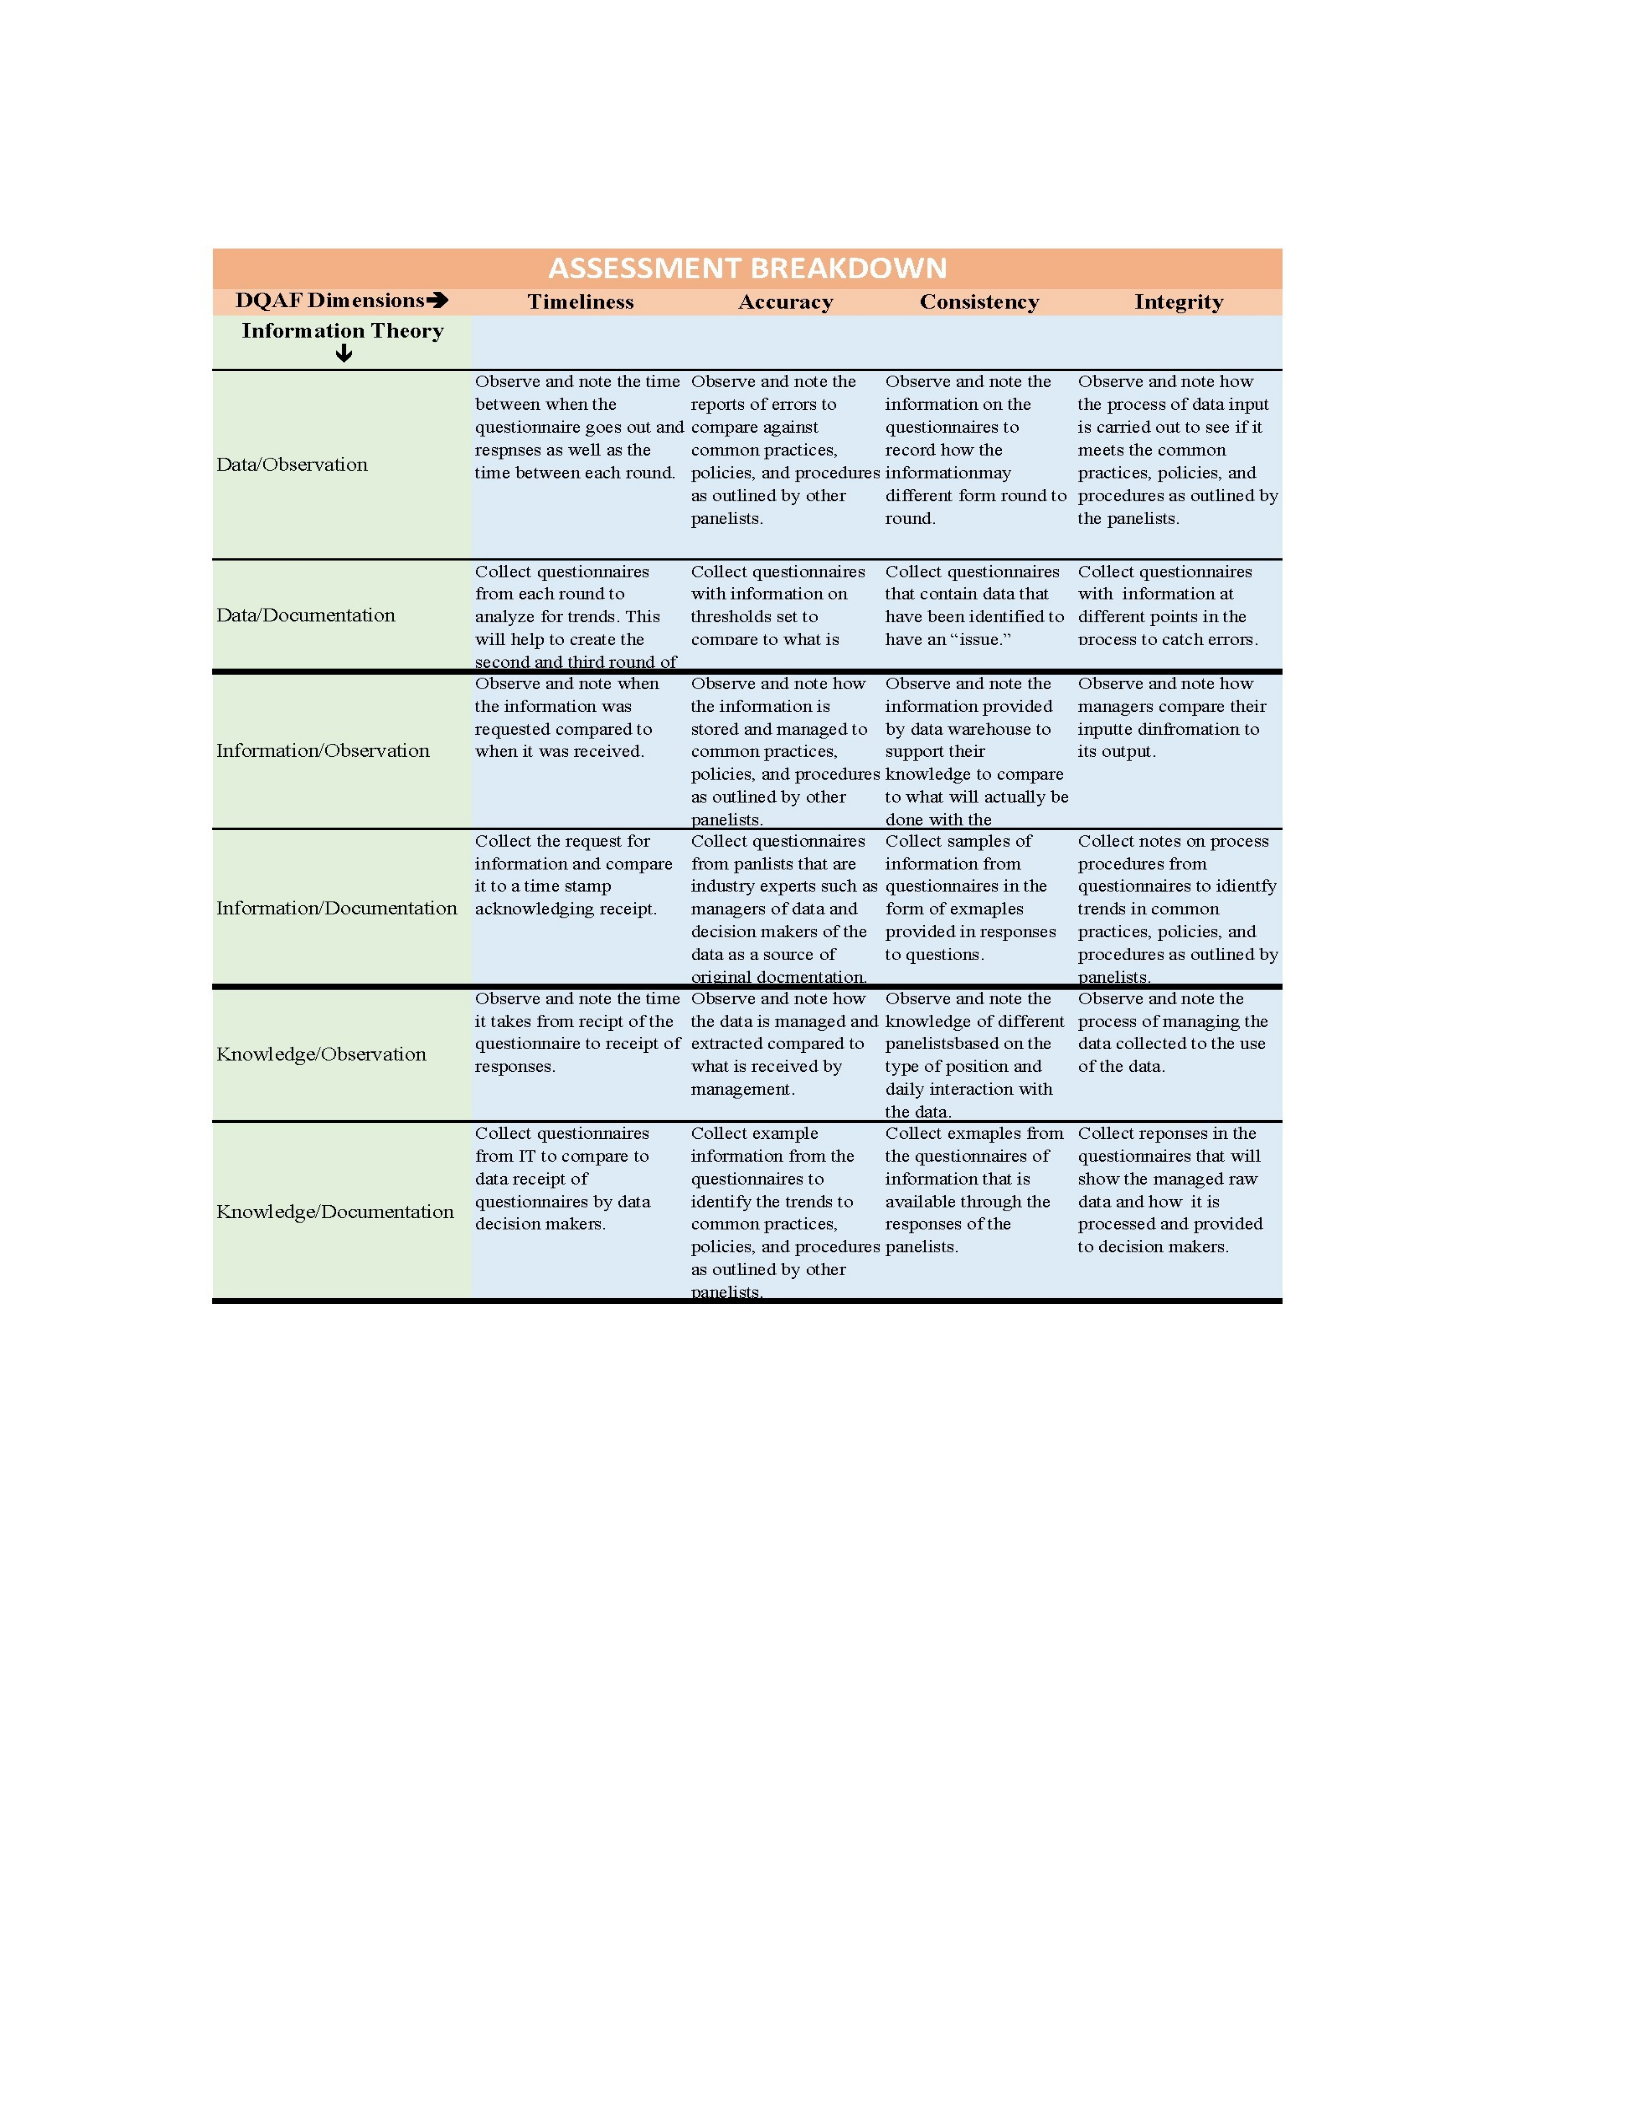
Figure 3. Assessment breakdown of how the data quality assessment framework and
information theory can be used to evaluate collected data. Adapted from DQAF
developed in 2003 by the IMF. Adapted from “Data quality assessment framework and
data quality program” by IMF, 2003,
http://www.imf.org/external/np/sta/dsbb/2003/eng/dqaf.htm. Copyright 2003 by the
International Monetary Fund.

Data Quality Assessment Framework (DQAF)
The DQAF is quickly becoming a useful tool for assessing data quality in
industries other than finance. Its main use is to reveal quality issues by finding anomalies
in data patterns within a system (Sebastian-Coleman, 2012). Although utilization of the
framework by Yang et al. (2014) was for a financial system, the assessments and
measurements created allowed researchers to improve standards for the system and use of
big data tools. Senkubuge et al. (2014) validated the use of the DQAF in their study on
health systems, health sector reform, and delivery of services as an assessment tool to
analyze data collected. Their study focused on two data quality dimensions, availability
and accuracy. They used accuracy as one of the data quality dimensions to qualify the use
and demand of information within the system under study. Although the creators of the
DQAF use validity in place of accuracy in their framework, accuracy was used in my
study.
In addition to the four data quality dimensions selected for this study, the DQAF
includes completeness. This dimension is a component of the dimension of Integrity (see
Appendix A) in my study as it is based upon the existence of data. Moreover, the
foundation of this study is the existence of the data, which is the general focus; therefore,
the dimension of completeness, rather than appearing to be omitted, is subsumed under
the dimension of Integrity.
Abdul-Hamid (2014) agreed that the use of the DQAF would yield structured
assessments to evaluate systems information. Abdul-Hamid used the following five data
quality dimensions: integrity, accessibility, accuracy, reliability, and serviceability. His

study found varying degrees of strengths and weaknesses in the quality of data and
decisions based on the data. Abdul-Hamid extended his study further than Senkubuge et
al. by using a situational analysis tool SWOT (Strengths, Weaknesses, Opportunities, and
Threats), and benchmarking, in conjunction with the DQAF to secure stronger results.
SWOT was developed in the 1960s as a technique to unleash an individual’s career
potential, but its principles are applied today as a problem-solving tool.
Data Quality Dimensions
Data quality dimensions and characteristics of data quality, which are often called
information quality dimensions, are used to create measurements for data quality. There
are 16 data quality dimensions, which are discussed in research (Wang & Strong, 1996).
However, just four of them are most often used by researchers as a guide to assess the
quality of data within an organization. Shankaranarayanan and Cai (2006), along with
Bray and Parkin (2009), conducted studies in which three of the most commonly used
dimensions of data quality, completeness, accuracy, and timeliness were used to test the
quality of data production. Although there were multiple ways to view the data from a
quality perspective, the authors found that decisions related to data processes influence
how data quality is perceived, thereby introducing subjectivity rather than consensus into
the results (Shankaranarayanan & Cai, 2006); Bray & Parkin, 2009). Data quality
dimensions provide a starting point for organizations to begin identifying and building
data quality measurement categories. Although there are over 200 data quality
dimensions addressed in research, in this study I will address the four most widely
discussed data quality dimensions among researchers on this topic. Abdul-Hamid (2014),

and Moghaddasi, Rabiei, & Sadeghi (2014) identified integrity, accuracy, consistency,
and timeliness as the four specific data quality dimensions used most frequently.
Information Theory
Ramírez-Gallego, Mouriño-Talín, Martínez-Rego, Bolón-Canedo, Benítez,
Alonso-Betanzos, & Herrera, (2018) found information theory to be a broad theory that
encompasses many different aspects and versions of what a theory is or could be. One of
the information theory models frequently used in health information/informatics systems
is the Blum Model. Blum (1986) demonstrated how medical informatics or clinical
information can be processed in a system as three categories: data, knowledge, and
information. This model eventually became the data, knowledge, information model to
which some researchers have added wisdom. Goossen (2014) used the model to draw a
connection in his study from human thinking and systems thinking with information from
an EHR.
The Evolution of Data Quality in Healthcare
The topic of quality in all of its dimensions is broad. From quality assurance to
data quality, countless scholars have written volumes on the nature of quality and quality
issues in their respective fields. However, a few might be considered as pioneers whose
writings are fundamental to most fields of study that embrace quality issues such as
Deming, Juran, and Shewhart.
Deming (1986) established the idea that system and employee performance
quality first arises from management, then progresses to other employees in the
organization with Total Quality Management. His approach leaned more toward a theory

of employee management than one of product and focused on incentives to improve
employee performance. This assumed that employee performance improvement would
refine the quality of the product.
One of the reasons his 14 points of managing were adapted to the healthcare
industry was to introduce management to a new way of thinking for assessing acceptable
levels of errors for ever-revising assessment protocols. Juran (1951) approached quality,
and the management of quality, through different areas of management processes, such as
planning, control, and improvement. Juran believed that proper training and management
of processes could result in lowering the cost of quality.
Shewhart (1939) believed that methods that yielded accuracy and precision of
quality outcomes should be deployed. Ivanov extended Shewhart’s theory regarding
minimizing errors, and the connection between data and information (SebastianColeman,
2012). One assessment method that emerged from the work of these early authors on
topics related to quality was Total Quality Management (TQM) developed in the 1950’s
by Deming and later expanded on by Shewhart (Joshi, Ransom, Nash &
Ransom, 2014).
In the 1980s, these ideas were extended with the introduction of Lean Six Sigma,
which sought to remove inefficiency by addressing timeliness and to solve business
process problems by reducing variations (Nave, 2002). In the 1990s, Harvard Business
School professors, Norton and Kaplan (2016), developed a strategy called Balanced
Scorecard to measure business processes, customer satisfaction, new ideas, and training
of personnel. All these approaches have been applied to data quality today. Their various

aspects have been used to create tools designed to address data quality problems currently
being discovered.
Gap in Literature
This study has the potential to addresses the gap in the lack of empirical studies on
data quality deficiencies or errors in health care EHR systems. Organizations recognize
the need for usable research to strengthen data quality. According to Holzinger, Dehmer
& Jurisica (2014), there is a need for future research for creating frameworks to identify
exceptions in data quality and to address the process used by humans and computers in
data manipulation. Shankaranarayanan & Blake (2017) posited that future data quality
research would require Using a predictive algorithm data mining model in a dataset to
assess the performance and manage quality within an EHR. This conclusion was
determined by utilizing a case study approach with supporting data from datasets.
Researchers have advanced vigorous and valid arguments to address unanswered
questions regarding the question “what are considered universal practices for handling
data quality problems within EHRs” (Joglekar, Anderson, & Shankaranarayanan, 2013)
Much of the research on data quality has become the mission of independent,
private, and government organizations, such as Healthcare Information and Management
Systems Society (HIMSS), Experian, National Institutes of Health (NIH), American
Society for Quality (ASQ), Agency for Healthcare Research and Quality (AHRQ) and
Gartner. The dearth of academic literature that addresses poor data quality suggests a
need for scholarly empirical research on this topic in order to inform healthcare

management in charge of digital record keeping of effective practices regarding records’
management and error prevention pertaining to EHRs.
Typologies of Data Quality Errors
Experian (2013) categorized data errors by developing a list of typologies. It
conducted a corporate study that identified duplicate entries as one of the major data
quality errors (p. 18). Hedt-Gauthier et al. (2012) identified duplicate entries and missing
information as data errors or flaws. McCoy, Wright, Kahn, Shapiro, Bernstam & Sittig
(2013) used a quantitative method with two hospitals and five locations in their search to
find an accurate number of duplicate records. Their study findings demonstrated a
variation in the percentage rates of input data errors, ranging from 16.49% to 40.66%,
with something as simple as the first and last name. When more variables were added,
errors decreased. Managing these duplications revealed differences in the process as well.
The purpose of this study was to identify duplicate records and find solutions to manage
them.
McCoy et al.’s (2013) addressed areas of concern that can be found in healthcare
records systems. The key finding in this article was that assessing practices for managing
duplicate information, managers could help to prevent duplications. McCoy et al also
addressed the importance of misspelled data as another deficiency of data quality.
Researchers reported only duplicate patient information yet failed to make a distinction
between obvious duplications and information that had the potential to become a
duplicate. This distinction was not based upon information that was used, which was the
demographic information of participants.

Berndt, McCart, Finch & Luther (2015) examined the data quality of all related
documents from an EHR system. The research used a case study method, which included
four hospitals with a dataset of 26,010 clinical progress notes. Researchers found that
error rates contained in the documents remained at the target rate of 30%, with a small
sample of 1,000. As the sample size grew, the error rate rose to 40%. The study was
conducted to test the text mining approach that is being used with free form text
documents to see how well it performs. The results of this study indicate weaknesses in
the data-mining approach. Simply identifying rates of errors by percentages fail to yield
meaningful information on patient outcomes. Results also revealed that a small sample
size is not a good indicator of data mining as a solution to data errors. Berndt, McCart,
Finch & Luther (2015) sought to find what common practices could be derived from text
mining. Their discovery of the number of errors that can be found in sample sizes
contributes to my question about a data quality threshold that an organization uses and
why. Because of this study, the authors “began to establish some guidelines when
choosing sample sizes in the face of target quality issues. These findings have particular
significance with regard to annotation efforts” (pp. 1,14).
Berndt’s et al (2015) study determined where the errors would start to appear in
the data. Among issues uncovered, misspelled words appeared with regular frequency.
This indicated a decline in quality but not the data quality characteristics that the authors
claimed had been addressed. A specific acknowledgment of data quality characteristics
May have highlighted those areas. Altwaijry, Kalashnikov & Mehrotra (2013) identified
missing values as one of the common data quality problem types. Their study consisted of

a quantitative analysis to show that a query-driven approach to data cleaning was more
effective than other commonly accepted practices or approaches. Kuehl et al. (2015) also
identified missing values as one of the most important data quality problems.
Tools to Address Poor Data Quality
De Almeida et al. (2013) described data as a critical part of any organization (p.
19). Data is a fundamental element of most organizations, whether small or large, that
keeps business moving in a forward direction. Data may come in many forms and its
importance will increase depending on the nature of a particular business. For example, in
healthcare, electronic patient data is highly important as it promises to streamline general
office practices such as setting up patient records, ordering tests, medications, and
treatments, among other tasks. Gunawan (2016) asserted that data within an EHR must be
protected and private according to HIPAA regulations (p. 7). Despite the importance that
the U.S. healthcare industry places upon the need for quality, poor and insufficient data
continues to be an obstacle for the delivery of superior healthcare.
Big Data Analytics was introduced as an early intervention tool to solve a range of
data insufficiencies in the business sector. Its application to data problems in the
healthcare industry provided an opportunity to address insufficiencies attributed to
processing health information in the form of raw data. Raw data are referred to as the
lifeblood of healthcare organizations, a collectively essential component of daily,
datadriven, decision-making processes across multiple institutional contexts (Foshay &
Kuziemsky, 2014). The quality and integrity of healthcare data are essential not only to
the overall provision of superior healthcare, but also to organizational effectiveness in the

delivery of care and services. Researchers in more than a few studies explored ideas on
the identification and management of data quality issues. Some researchers
(AdlerMilstein &Jha, 2013; Schultz, 2013; Foshay, & Kuziemsky, 2014; Chen, Chiang,
& Storey, 2012) attempted to remedy some data quality issues with BI tools in the form
of big data. A few researchers sought to mitigate data quality issues with an EHR
implementation and to meet government requirements in order to receive incentives
(Charles, Gabriel, & Furukawa, 2014).
Superior data quality and integrity remains an important goal within the U.S.
healthcare system. As most healthcare organizations transition to EHRs, data quality
management has become a critical area of focus (Jamoom et al., 2014). The many
challenges regarding data quality include potential inaccuracies and fragmentation
(Adler-Milstein & Jha, 2013). Holzinger, Dehmer, & Jurisica (2014) conducted an
overview of data quality errors that currently exist and offered suggestions for handling
them now and in the future. Rather than list errors and solutions, Holzinger et al
addressed what frameworks should be considered as most useful when determining how
to solve data and management errors. Holzinger, Dehmer, & Jurisica (2014) stated, “We
need machine intelligence to deal with the flood of data, but at the same time we must
acknowledge that humans possess certain problem solving and cognition abilities far
beyond computation” (p. 7). They showed areas of data workflow process managers find
most challenging regarding data quality deficiencies and their solutions. In the article, it
was demonstrated that universal workflow guidelines are considered and/or used as
solutions for data quality problems.

The application of Big Data analytics as a solution to poor data quality was
followed by the introduction of several other textual analysis tools that looked promising.
QNOTE was one such tool. Burke et al. (2014) conducted a quantitative study to
determine if a tool called QNOTE (according to the National Institutes of Health QNOTE
is not an actual acronym, but rather a valid name for a tool that evaluates EHRs) was an
accurate gauge to measure the quality of data in clinical notes. Burke’s (2014) study used
300 clinical notes from 100 outpatients and applied QNOTE, which had 12 variables, to
score the quality of clinical notes. Researchers found that QNOTE excelled in measuring
the quality of data within the study’s clinical notes. This article (Burke et al., 2014) is
relevant to my study because it supports the lack of empirical studies on data quality tools
and solutions.
Chen, Chiang & Storey (2012) used a quantitative study to find challenges to
using BI and analytics. The purpose of the study was to introduce “next steps” and inform
the academic community of the need for research on BI and analytics. The study
commenced with 6,187 papers and ended with 3,602 after removing IT publications and
journal articles retrieved from databases such as Science Direct and PubMed.
Researchers discovered that even with a substantial increase in the use of EHRs and the
introduction of big data analytics, a lack of scholarly research remains on data analytics.
Cusack, Hripcsak, Bloomrosen, Rosenbloom, Weaver, Wright, & Mamykina (2013)
examined how redundant data could be considered a data quality error. Cusack et al.,

2013 conducted a study during a professional meeting that engaged 100 participants in
breakout sessions to create action items for discussion. These breakout sessions resulted
in multiple findings and recommendations.
The purpose of data capture and documentation, in conjunction with business
areas within healthcare organizations to be supported, was acknowledged as important to
understanding data workflow practice (Cusack, et al., 2013). Cusack, et al (2013) also
found that benchmarks are necessary to evaluate data capture and documentation
processes. They concluded that data capture and documentation should not result in
diminished workflow activities and delivery of care but should only support the processes
that take place daily. These findings affect judgments of end-users (management) and
their abilities to render quality patient care based on EHR data. Study benchmarking and
assessing information for data quality and data quality management, highlights what is
currently being discussed as data quality problems within the healthcare industry. They
also addressed decision-making as an outcome of captured data within an EHR system.
One key finding was that different areas within a healthcare organization have different
workflow patterns and daily activities to consider when using an EHR system, given that
patient safety is the overarching goal of a record keeping system. To that end, a core
connection from the article was the relationship of electronic data capture and
documentation processes and practices to patient safety and quality of care.
Quality of care related to healthcare data has implications beyond data input,
patient and physician portals, and record keeping. Healthcare providers routinely access
digital records for diagnostic purposes, specialists’ referrals, and changes to patient

prescriptions, and other reasons. Records access by healthcare providers anticipates
action for the benefit of patients and constitutes what is commonly called secondary use
of patient information (Church, 2002). Kwon, Lee & Shin (2014) used a survey driven
quantitative study to discover if the advantages of data quality use and management has
been a considered factor for adopting big data analytic tools. Researchers applied the
research-based view theory to a survey that was disseminated to 969 organizations (306
respondents). They found that organizations that were ready to make well-planned
decisions with their secondary data were more apt to invest in resources like big data
analytics. This article supports my study because of its focus on the secondary data that
were used to make decisions without needed tools for managing data quality.
Taggart, J., Liaw, S., Dennis, S., Yu, H., Rahimi, A., Jalaludin, B., & Harris, M.
(2012) extracted patient data from four practices to complete their quantitative study. The
purpose of that study was to identify data quality problems within an electronic healthcare
system. Using a registry from which they had extracted data, researchers found that data
regarding gender and date of birth were substantially incomplete and even that high levels
of inconsistencies and incomplete records appeared to be routine occurrences. Further, it
suggested the possibility of establishing best practice guidelines to address these obstacles
to good data. They also examined the perspective of data capture and the use of the
information within the system as secondary use.
Effects of Poor Data Quality
Healthcare organizations are negatively affected by poor data quality.

Deciphering the impact of poor data quality within the field of healthcare suffers from a
lack of agreement on the part of academics (researchers) as to which dimension of
healthcare is most adversely affected. Foot et al. (2014) emphasized that community
services were affected by the poor quality of healthcare information (p.2), while
Debbarma, Nath & Das (2013) found that the greatest negative impact to superior
healthcare delivery was poor decision making resulting from bad data. Judah & Freidman
(2014) agreed that poor decision-making was a factor and extended the discussion of
impact to include organizational costs.
Summary and Conclusions
Chapter 2 contained a review of literature related to an analysis of information
theory and DQAF. Based on the literature review, there appears to be a breakdown in the
process that occurs with data quality. Major themes in the literature base were the
evolution of data quality from quality and improvement management, data quality
dimensions and the methods to assess data quality, a data quality assessment framework
to measure common or routine data-related practices in use by healthcare organizations,
data information, Blum Knowledge model used in health informatics.
Chapter 3: Research Method
Introduction
The purpose of this Delphi study was to identify best practices in data quality and
integrity in healthcare. This study took place over a period of 4 months and was
conducted with three rounds of questions for a panel of IT and non-IT data experts. These
panel of experts were chosen based upon their ability to provide information based on

their current connection to working with and managing healthcare data. A sample of 25
IT and non-IT data managers who met the inclusion criteria identified in this chapter was
used. Those data managers were system managers responsible for oversight of the
manipulation and maintenance of healthcare. The experts were recruited from sources
such as LinkedIn and Trade associations.
Research protocols for this study included a structured open-ended questionnaire
in the first round, followed by two rounds of mixed structure questions using
dichotomous, Likert, and scaling ranking strategies. The results from the first round drove
the questions for the second round. After analyzing the results from the first round, the
second round of questions were created. The third round of questions were similarly
generated. The process of data collection and healthcare data management best practices
was the focus of the data quality evaluation.
This chapter on the research design consists of six major sections: (a)
Introduction, (b) Research Design and Rationale, (c) Role of Researcher, (d)
Methodology, (e) Issues of Trustworthiness, and (f) summary. In Section 1, I provide a
synopsis of the research study and its purpose. Section 2 addresses how the research
design and methodology applied to the research question. In Section 3, I provide an idea
of the role I played within the study as well as an overview of my prior experiences
within the field of healthcare practice. In Section 4, I will outline the methodology—
participants, instruments, pilot study and recruitment. In Section 5, I examined issues of
trustworthiness such as ethical procedures and credibility. In Section 6, I provide a
summary.

Research Design and Rationale
This study was guided by one essential question:
Research Question: What practices contribute to identifying improvements in
EHR data collection, secondary use of data, data quality, and integrity?
Role of the Researcher
My role as the researcher was to distribute and collect surveys from the
participants and to analyze collected surveys. In the Delphi study, I developed the
subsequent round questions based on the responses of the previous round (see A. von der
Gracht & Darkow, 2013). A. von der Gracht and Darkow (2013) stated rules that a
researcher should follow when conducting a Delphi study: eliminate obscure questions
and use correct industry terminology and clearly stated guidelines.
Throughout the research process, I performed all actions necessary to acquire the
data that were used to formulate each round of questions. I had no personal connection to
any of the panelists selected for this study. Potential researcher biases and/or power
relationships were managed through the anonymity of all study participants. Once
selected, participants were given identification numbers, and all their responses were kept
confidential. Other potentially ethical concerns addressed would be the offer of incentives
for participation and/or conflict of interest among participants.
Method
A Delphi approach was the most appropriate methodology for this study. Ponto
(2015) discussed the use of open-ended questions to allow respondents to provide a
distinct response to a question. Respondents have the freedom to state their most honest

opinion on a topic based on experience, which will produce exploratory data that may
reveal unpredicted opportunities and/or issues.
Open-ended questions generate information that is useful in suggesting ways to
format questions and select study participants as might prove appropriate (Ponto, 2015).
Qualitative research surveys have been used to gain a more thorough understanding of a
person’s underlying thinking and incentives of a topic, issue, or problem (Ponto, 2015).
The focus of this study was on the issues that precipitate data quality errors and a
consensus of best practices used to manage them as seen through the eyes of the IT data
stewards within the healthcare industry.
The Delphi method was developed in 1944 and later refined in 1950s by the
RAND Corporation. The method was created as a technological forecasting tool. It is
applied by gathering a group of unidentified experts to complete surveys through a series
of three or more rounds (Sekayi & Kennedy, 2017). The objective is to create a consensus
in thinking among the panelists (Sekayi & Kennedy, 2017). This study followed the
accepted Delphi method practice and protocol. McMillan, King, & Tully
(2016) asserted that data collected from a survey in a Delphi method are strengthened by
the ability of the researcher to assist in creating robust guidelines; although conversely,
Brady (2015) found that using this method yielded inconsistent data from surveys due to
how an expert is determined when creating a sample, questions on bias, and the lack of
perceived correct answers or opinions acquired from the consensus. Despite controversial
perspectives regarding the value of Delphi method results, findings may reveal
information about participants that could be overlooked in a quantitative method.

Participant Selection
The multiperspective population consisted of 25 different healthcare systems data
management professionals, also known as data stewards, across the United States who
have worked or are working for a healthcare system such as an EHR and have managed
the data within this system over a period of 5 years. Participants were recruited from
sources such as LinkedIn, trade associations, and networking. The panelists were chosen
using a purposive sampling technique. The criteria included professional level experience
with healthcare data and IT or non-IT position with data quality. I preferred that the
panelist was currently working with data.
The rationale for using a purposeful sample in a qualitative Delphi method study
was to obtain results that provided a general picture of the research problem, such as what
data quality issues have been identified and how they are managed in their respective
organizations. Potential research panelists were contacted and provided with a complete
outline of the study. Members of the sample population were selected based upon their
current position and knowledge of data process and best practices currently being used.
All participants received a consent to participate form.
During the survey, participants were asked a series of open-ended questions and a
mix of dichotomous, Likert, and scaling questions that allowed me to obtain data about
their assumptions of quality issues and current data handling practices. This form of
questioning produced reliable comparative data. Open-ended questions have been shown
to be the most appropriate form of questioning when encountering complex or convoluted
answers (Fowler, 1995). This line of questioning is also advantageous in measuring the
knowledge of participants (Fowler, 1995). All questionnaires were collected, analyzed,

and augmented through note taking. The resulting information was reviewed for themes
or patterns in order to produce raw data for analysis.
Instrumentation
The participants were asked to answer four open-ended questions (See Appendix
A) in the first round of the study. Surveys were administered via Survey Monkey. Figure
4 shows the data collection plan.
Figure 4. Data collection plan.
Survey Monkey was used to distribute and collect the survey responses. I took notes
during my analysis and coding of the data using Microsoft Excel and OneNote document.
Collected surveys were compared and cross-checked. A unique survey number and code
was used to identify each participant and survey. One unforeseen challenge that would
have required a follow-up request might be responses that are not clear or responses that
are after thoughts. Another unforeseen challenge would have been participants not

wanting to answer certain questions. I noted and described the missing responses in my
analysis.
Field Test
Field test are integral components of research studies. Clow and James (2014)
asserted that a field test can produce results that can assist the researcher in finding ways
to strengthen their measurement tool for gathering necessary data. A field test of the
open-ended questions to strengthen the responses received from participants took place
with three healthcare IT managers not included in the overall study.
A field test was conducted with the proposed Round 1 questions to test their
validity. Field test of interview/Round 1 questions are a common practice. Three
healthcare IT professionals evaluated the questions for efficacy. These experts were not
included in the study. Initial drafts of the questions were revised based on the expert’s
input.
Data Analysis Plan
Each participant was assigned an identifier code to protect their anonymity. A
Survey Monkey link including the first round of open-ended questions was emailed to the
selected panelists. This survey included the directions, the due date, and how to handle
any questions the panelists might have incurred.
Round 1 responses were entered into an Excel spreadsheet and Microsoft
OneNote document to look for trends and patterns. Once a significant number of themes
were found, the Round 2 questions were created. These questions were sent to the
panelists through Survey Monkey with directions. These questions did not include a space

for additional information. The responses were collected. In addition to trend spotting,
this round of questions consisted of a Likert scale, and a simple frequency distribution
statistical method was used to analyze the responses (see Sullivan & Artino, 2013). A
third round of questions was created and distributed in the same manner as the first two
rounds. The final analysis consisted of a feasibility scale to determine the consensus
among the group (see A. von der Gracht & Darkow, 2013).
Trustworthiness
In qualitative research, issues of trustworthiness include credibility,
transferability, dependability, confirmation, and ethical procedures. These areas are
fundamental to the concept of validity, as they help to ensure that areas of conflict or
inconsistency may be eliminated or at the least minimized. Triangulation was used to
assure the validity of information. I also keep detailed notes on all steps of my research
process.
Credibility
Credibility refers to the extent that the results are valid and reliable and
confirmable. Several approaches were used such as data saturation (Padgett, 2012),
triangulation and transparency using field notes. Triangulation was accomplished using
methodological triangulation, which includes the use of document, such as the literature
review, and field notes. Triangulation is useful in minimizing procedural and sampling
bias (Rowe, Frantz, & Bozalek, 2013).

Dependability
The process of the study was reported in detail to allow for the attempt at
recreating the same results. This will also allow the future researchers to assess the
validity of the methods used in this study. These actions will also establish
trustworthiness.
Confirmation
Although all data will be analyzed objectively, other researchers would not be
able to arrive at the same results using an equivalent methodology. I presented the data in
the same order in which they were collected and analyzed. I documented the details of the
process of data collection, data analysis, and interpretation of the data. I also documented
what topics were found to be distinctive and interesting during the data collection, as well
as any specific thoughts and/or rationale about coding.
Ethical Procedures
Ethical concerns relating to non-identification of persons contained in surveys
were managed by assigning codes to participants. An informed consent letter containing
the IRB approval number (10-12-18-0070966) was sent to each participant. Appended
also to the request forms were the documents to allow participant refusal of participation
or early withdrawal from the study. Conflicts of interest, as well as relationship
boundaries, were addressed in the consent form for each participant. All participants were
allowed to withdraw from the study at any time. Participation were based upon a genuine
desire of panelists selected to be a part of the healthcare industry’s electronic data
improvement plan.

Research documents were secured on my password-protected computer. The
documents will be destroyed in three years. Data collected by Survey Monkey will be
stored on their servers. Please see Appendix B for an outline of SurveyMonkey
information for the IRB.
Preserving Participant Identity
The participants were assigned a code by SurveyMonkey to protect their identity,
which maintains robust data security with restricted research account policies. Only the
researcher will know who participated and any connecting background information. The
participant were referred to by their assigned code throughout the study and on any
reports generated form the student. During analysis the participants code was used to
identify their responses. Anonymity remained throughout the study.
Summary
This chapter has described the proposed research methodology to be used to
collect and analyze data obtained from participants in order to examine and evaluate
routine practices for EHR data quality and integrity management in healthcare
organizations. A qualitative approach for this study will entail a field test of the first
round of questions with due refinements to help ensure usefulness and validity of the final
study questions. A data analysis plan was developed to ensure a workable timeline for
data to be collected and analyzed. Chapter four will disclose the findings from the study,
with conclusions and recommendations for further research addressed in chapter
five.

Chapter 4: Results
The purpose of this qualitative Delphi study was to identify best practices for data quality
and data management in healthcare systems. I further identified the best practices to
include in guidelines for data quality and data management. This study was guided by one
essential question: What practices contribute to identifying improvements in EHR data
collection, secondary use of data, data quality, and integrity? In this chapter, I present the
results of the study in seven sections.
Field Test
The field test was conducted using three participants who were not included as a
part of the study. The participants were presented with the questions I planned to use in
the first round of my Delphi study and had 5 days to respond. The expected scope of
participation for the field test was explained to the participants, and prior agreement to
participate was acquired. The purpose of the study was explained as well as my
expectations from the field test. The following questions were provided for the field test
participants to answer as part of their review:
• Are these questions written clearly?
• Would you feel comfortable answering the questions?
• Is the time reference clear to the respondents?
• Would any of the questions require the respondent to think too long or
hard before responding? If so, which ones?
• Do any of the questions generate response bias? If so, which ones?
• Is the survey too long?

• Have any other important issues been overlooked?
The first round of open-ended questions were revised to address responses such as
specificity, assumptions of poor data quality, the use of techniques vs. strategies, removal
of certain words such as some, and clarifying terms used such as fitness of data.
Setting
The study was administered in the United States with participants in IT and nonIT
data positions and considered experts in their field. All communication with participants
was by email, such as survey distribution, reminders, follow up reminders, and thank
yous. Agreement and confirmation of participation were sent and received between
10/15/18 and 1/16/19 to a combination of 90 organizations and individuals of which 24
agreed to participate by completing an informed consent document in reply to my
invitation email. Not all 24 participants completed each of the three rounds of data
collection. There were no personal or organizational conditions that influenced
participants or their experiences at the time of the study that would influence the
interpretation of the results because all participants completed the survey at their leisure
where they felt they were in a comfortable environment and where they could concentrate
and take their time. This setting was highly encouraged in the survey invite.
Demographics
Participants involved in the study were selected based on professional level
experience with healthcare data and IT or non-IT position with data quality. I preferred
that the panelist was currently working with data within the healthcare setting. The virtual
panel of IT and non-IT data experts was chosen based upon their ability to provide
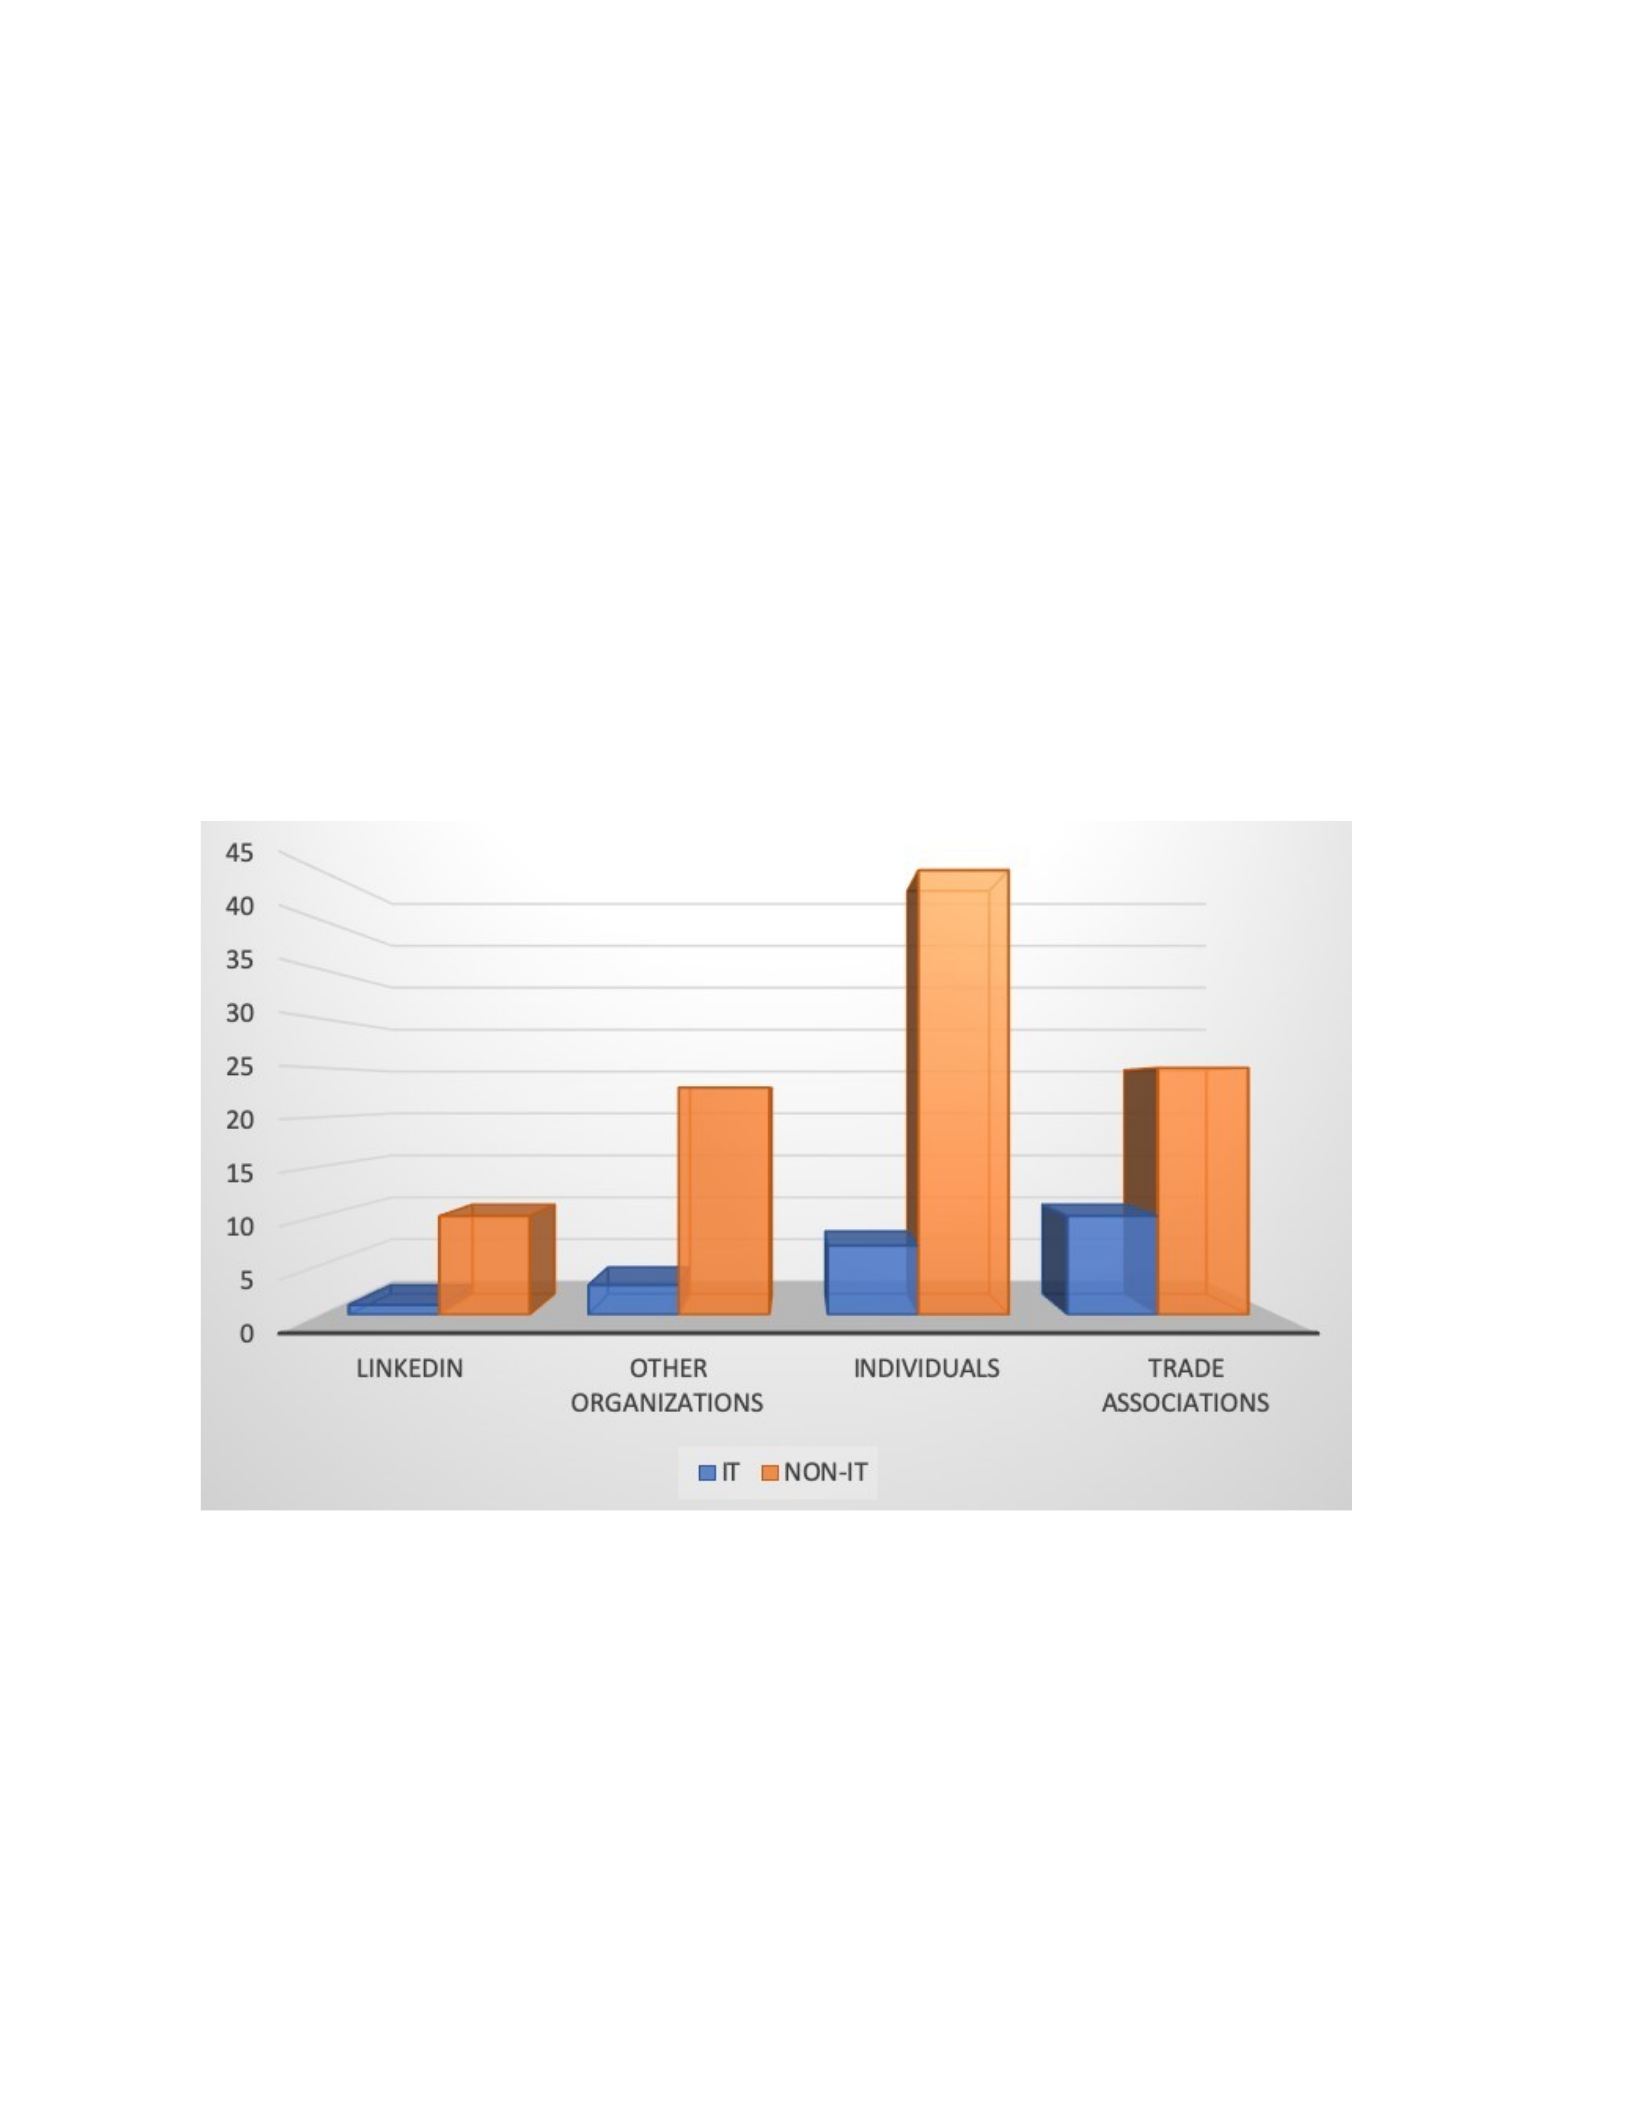
information based on their current connection to working with and managing healthcare
data. The data managers were system managers responsible for the oversight of the
manipulation and maintenance of healthcare data. The experts were mostly recruited from
word of mouth colleagues found on LinkedIn. Trade associations and other organizations
as well as individuals were contacted. Figure 5 shows the breakdown of the demographics
for recruiting participants. There is a bar to show the IT and the non-IT potential
participants who were contacted from the four different categorical groups.
Figure 5. Breakdown of demographics for recruiting participants.
Data Collection
This study consisted of three rounds of survey questions distributed to a panel of
IT and non-IT healthcare data experts who met selection criteria identified in Chapter 3.

Initially, I sought to include 25 participants, and the first round of questions was
distributed to 24 participants, of which 17 responded. Round 2 yielded 14 responses of
the 24 surveys sent. The same number of surveys were completed in Round 3, which was
14 out of 24. The survey was monitored daily once it was sent out by installing the
SurveyMonkey application on my mobile phone and tablet and turning on notifications. I
also had my inbox notifications on so that I would receive email alerts whenever a
participant had a question or completed a survey.
Round Details
Round 1 included four open-ended questions distributed via SurveyMonkey to 24
participants. One email invitation collector was created to capture which participants
completed the survey (17), opened the survey (22), and had not opened the survey (2).
There were no partial surveys included. In Round 2, a matrix of dropdown menus
question type was used that included four pages of general questions and a list of choices
ranging from strongly disagree to strongly agree for the participant to choose from. Each
page contained 18 to 22 statements to be ranked. This survey was distributed via
SurveyMonkey to 23 participants. One email invitation collector was created to capture
which participants completed the survey (14), opened the survey (18), and had not opened
the survey (5). There were no partial surveys included. In Round 3, a ranking question
type was used that included seven pages with general directions. There was one partial
survey included. The participants were given a 2-week deadline date explained at the
beginning of the survey and the survey email. A reminder email was scheduled to go out
7 days after the start of the survey clock. A day before the survey was scheduled to close,

I went in to see which participant had not completed the survey and sent him or her
second reminder. This sparked a few participants to look in their spam or request the
survey be resent as they could not find the original survey. The IRB received and
approved all questions for each round before the survey was distributed.
Data Analysis
Round 1
In Round 1, the participants were asked to answer four open-ended questions. A
list of words that emerged as themes throughout the responses was derived by using the
SurveyMonkey word cloud feature, which allowed for a search through all the responses
to create the word cloud based on the words found most often in each response for each
question. Table 4 illustrates the questions, words found, and the percentages. Figures 6 to
9 are the four questions asked in the survey and the resulting word cloud. Table 4
includes a breakdown of the Round 1 survey results and the percentage for the words
found the most form the results.

Figure 6. Single word cloud for all questions.
Table 2
Round 1 Survey Results Used to Identify Themes for Round 2 Questions
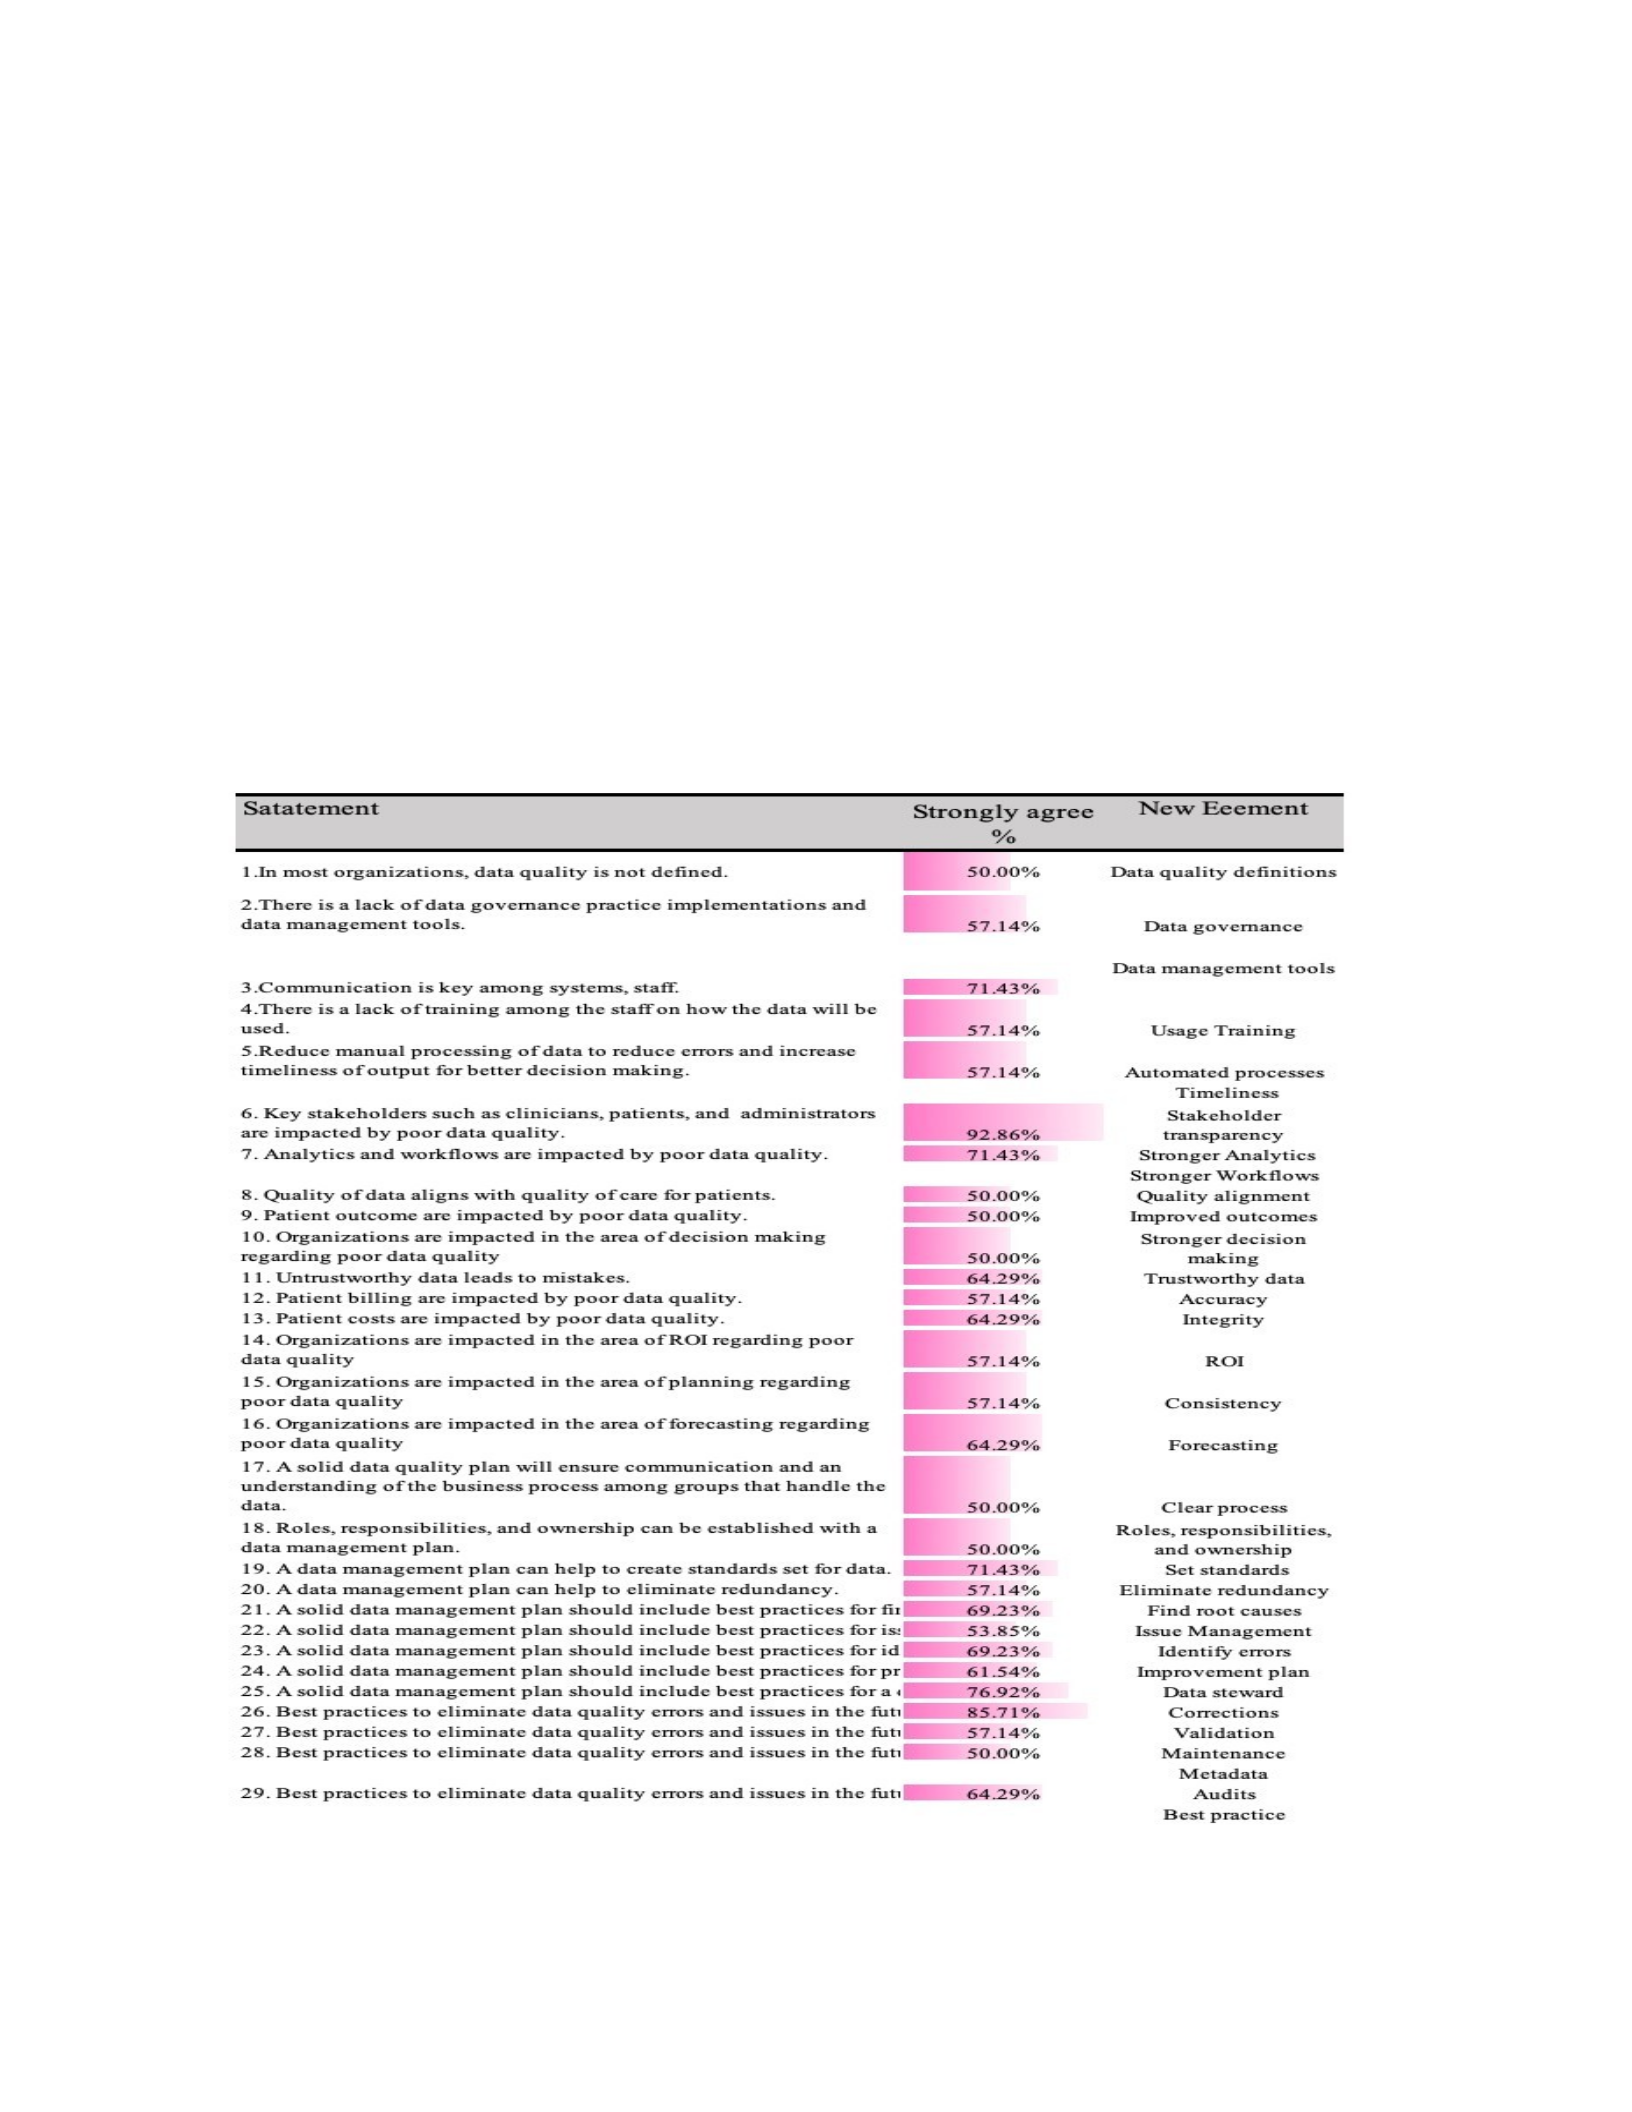
Round 2
To extract best practices that were most representative of the data, statements with the
highest ranking in strongly agree at 50% or higher was used. Table 5 shows the
statements, the percentages, and the best practices derived from the statements for Round
3.
Table 3. Round 2 Survey Results

There were no statements in which the participants unanimously strongly
disagreed. There were statements in which the participants ranked high in slightly
disagree and neutral. They were as follows:
•Best practices to eliminate data quality errors and issues in the future includes
implementation of lean Six Sigma continuous improvement, 35.71% Neutral
•Information generated from the poor data is often considered "unusable" because
of fragmentation, 35.71% Neutral
•Healthcare data quality is missing regulatory input, 42.86% Neutral
•Data sources should be limited for consistency and to avoid duplications, 21.43%
Slightly and strongly disagree. There were 29 statements used to transform into
33 best practices. Some statements formed two best practices. Any statement that resulted
in a duplicate best practice was not included. Two participants emailed after they had
completed their survey indicating they wished this round was also open-ended as they had
more to say. For example, participant DQS012 stated:
I would have loved to engage qualitatively around why I answered
some of these questions the way I did – some of the best practices
you touch on is very valid for a best practice, but some of it is also
very much linked to the maturity of the system in question.
Round 3
In round 3, the participants were asked to rank the five best practices provided in
each question on a scale of 1-5, with 5 being the highest. Some participants indicated that
it was difficult to rank because there were so many, they felt should be ranked the

highest. The themes found to rank closest to 5 were: usage training, timeliness, clear
processes, eliminate redundancy, corrections, and audit. There was a tie between quality
alignment and stronger decision making in question 4 (3.71) in which the lowest standard
deviation was used (1.28 and 1.03) to break the tie. The themes found to rank closest to 1
were: data quality definitions, automated processes, trustworthy data, integrity, Roles,
responsibilities, and ownership, validation, and metadata. Below you will find figures 713
showing each question along with the weighted average, and standard deviation for each
ranked best practice.
Figure 7. Round 3 survey results for Q1.

Figure 8. Round 3 survey results for Q2.
Figure 9. Round 3 survey results for Q3.
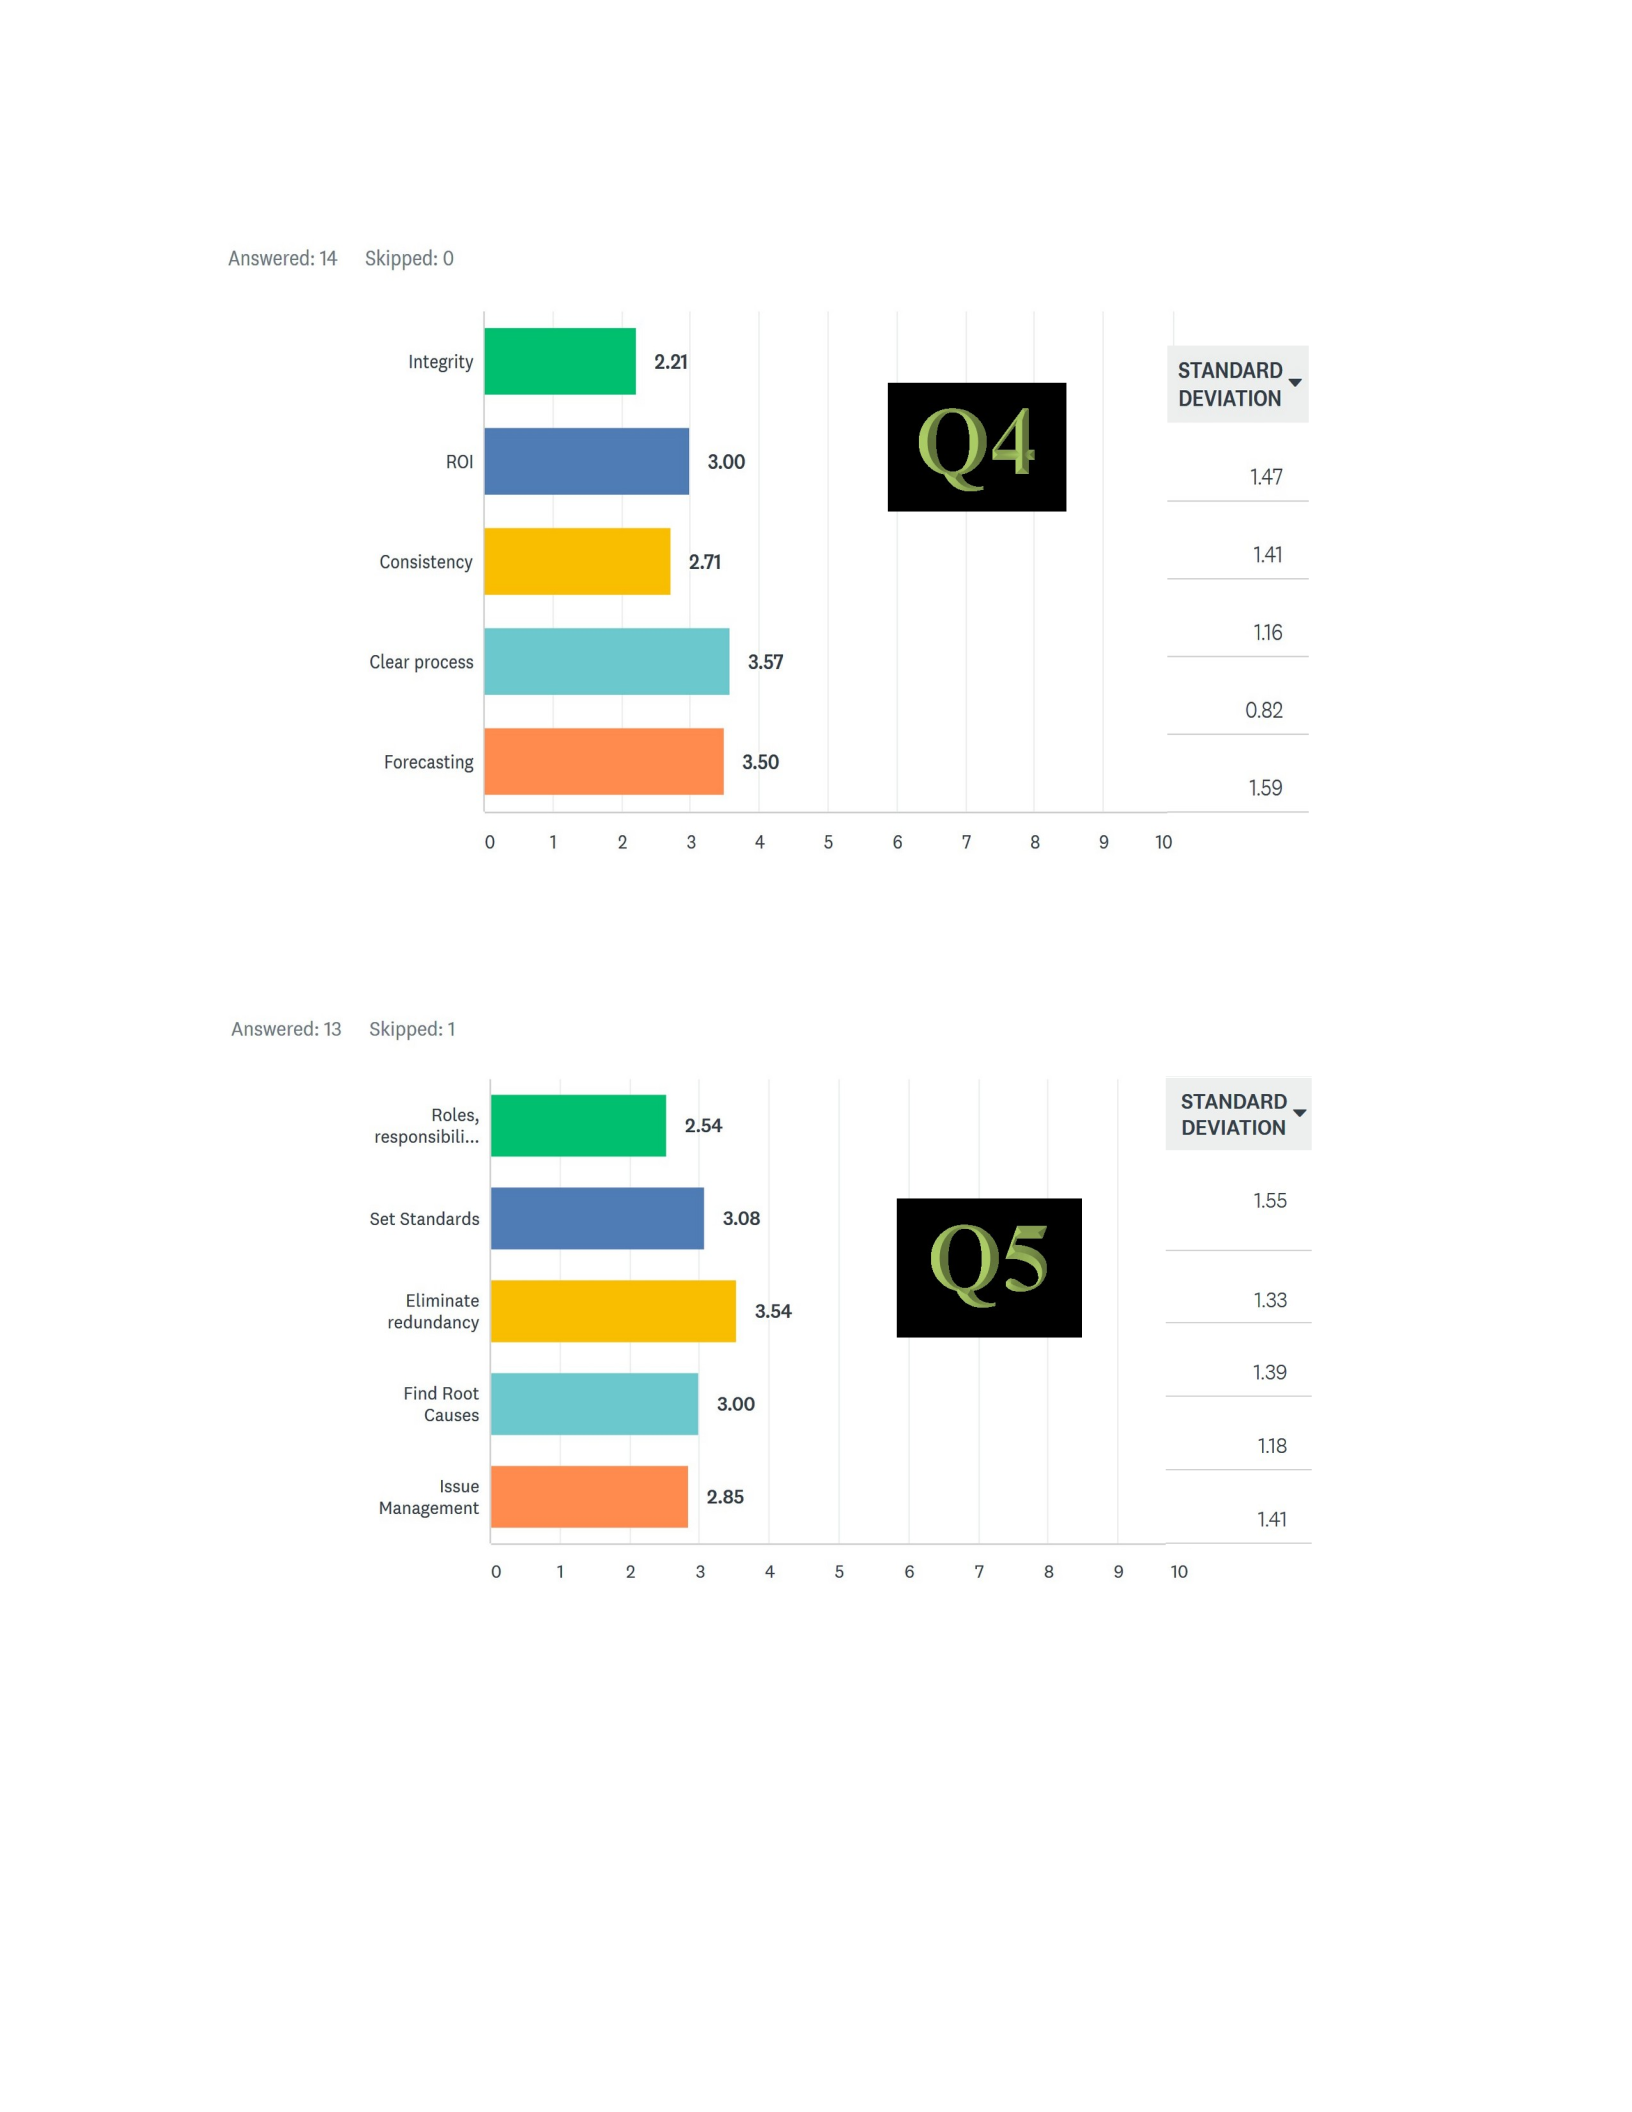
Figure 10. Round 3 survey results for Q4.
Figure 11. Round 3 survey results for Q5.
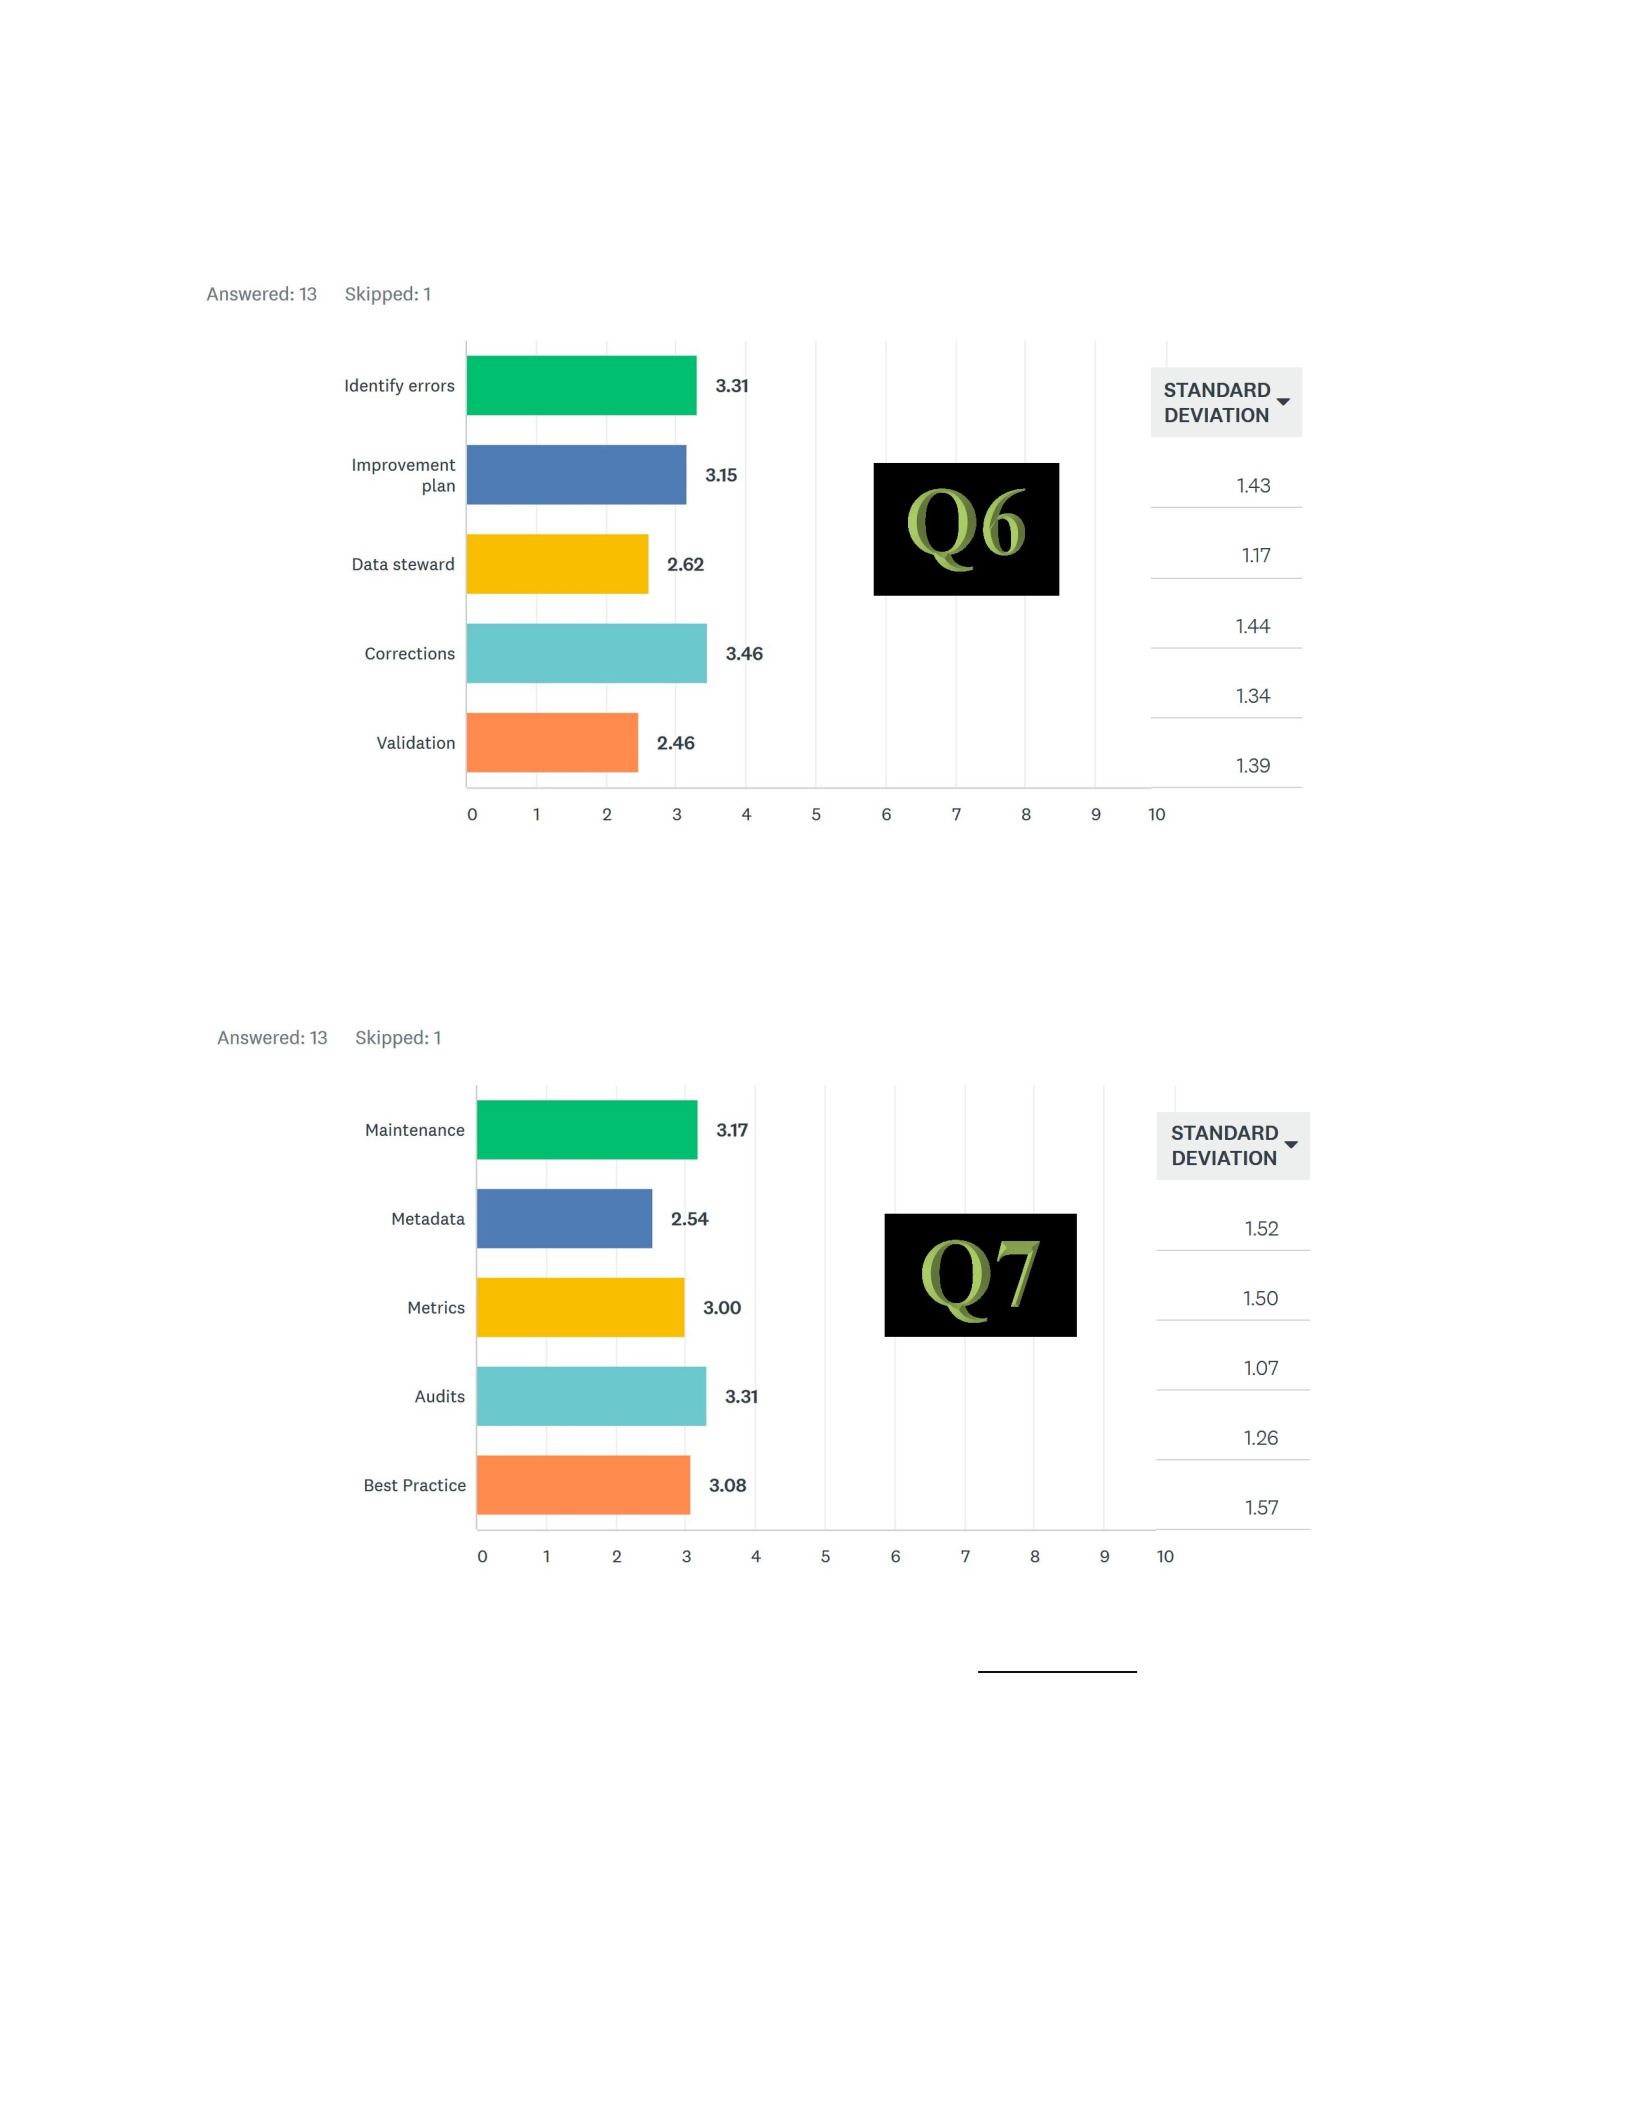
Figure 12. Round 3 survey results for Q6.
Figure 13. Round 3 survey results for Q7. Where is the chart Evidence of
Trustworthiness

Issues of trustworthiness were addressed by adhering to credibility, transferability,
dependability, confirmation, and ethical procedures. These areas were important to ensure
validity of the data collected and to eliminate chances of conflict or inconsistency.
Triangulation was used to also assure the validity of information by using open-ended
questions, Likert scale ratings of statements, and best practice rankings.
Detailed notes were kept on all steps of my research process.
Credibility
Credibility was achieved by identifying data saturation in each round. When
duplicate information stated to emerge, the search for themes was ended. In addition,
triangulation was used by implementing different survey types. Participants were from
different parts of the country and held different IT/Data positions. Each survey type
yielded the same or similar conclusions about the data. Transparency was achieved by
transferring my field notes to the study. Participants were from different parts of the
country and held different IT/Data positions.
Dependability
The process of the study was reported in detail to allow for the attempt at
recreating the same results. This will also allow future researchers to assess the validity of
the methods used in this study. These actions will also establish trustworthiness.
Confirmation
All data collected is documented along with the details of the process of data
collection, data analysis, and interpretation of the data. Topics that were found to be

distinctive and interesting during the data collection, as well as any specific thoughts
and/or rationale about coding were documented.
Results
Using the Data Quality Assessment Framework (DQAF), there were some
patterns identified of best practices that should be included to maintain or create best
practices for data quality.
Significance
Five best practices ranked highest throughout all the rounds. They were usage
training, timeliness, clear processes, eliminate redundancy, corrections, and audit. There
was a tie between quality alignment and stronger decision making in question 4 (3.71) in
which the lowest standard deviation was used (1.28 and 1.03) to break the tie. A bar chart
of the best practices that ranked highest in round three can be found in Figure 14.
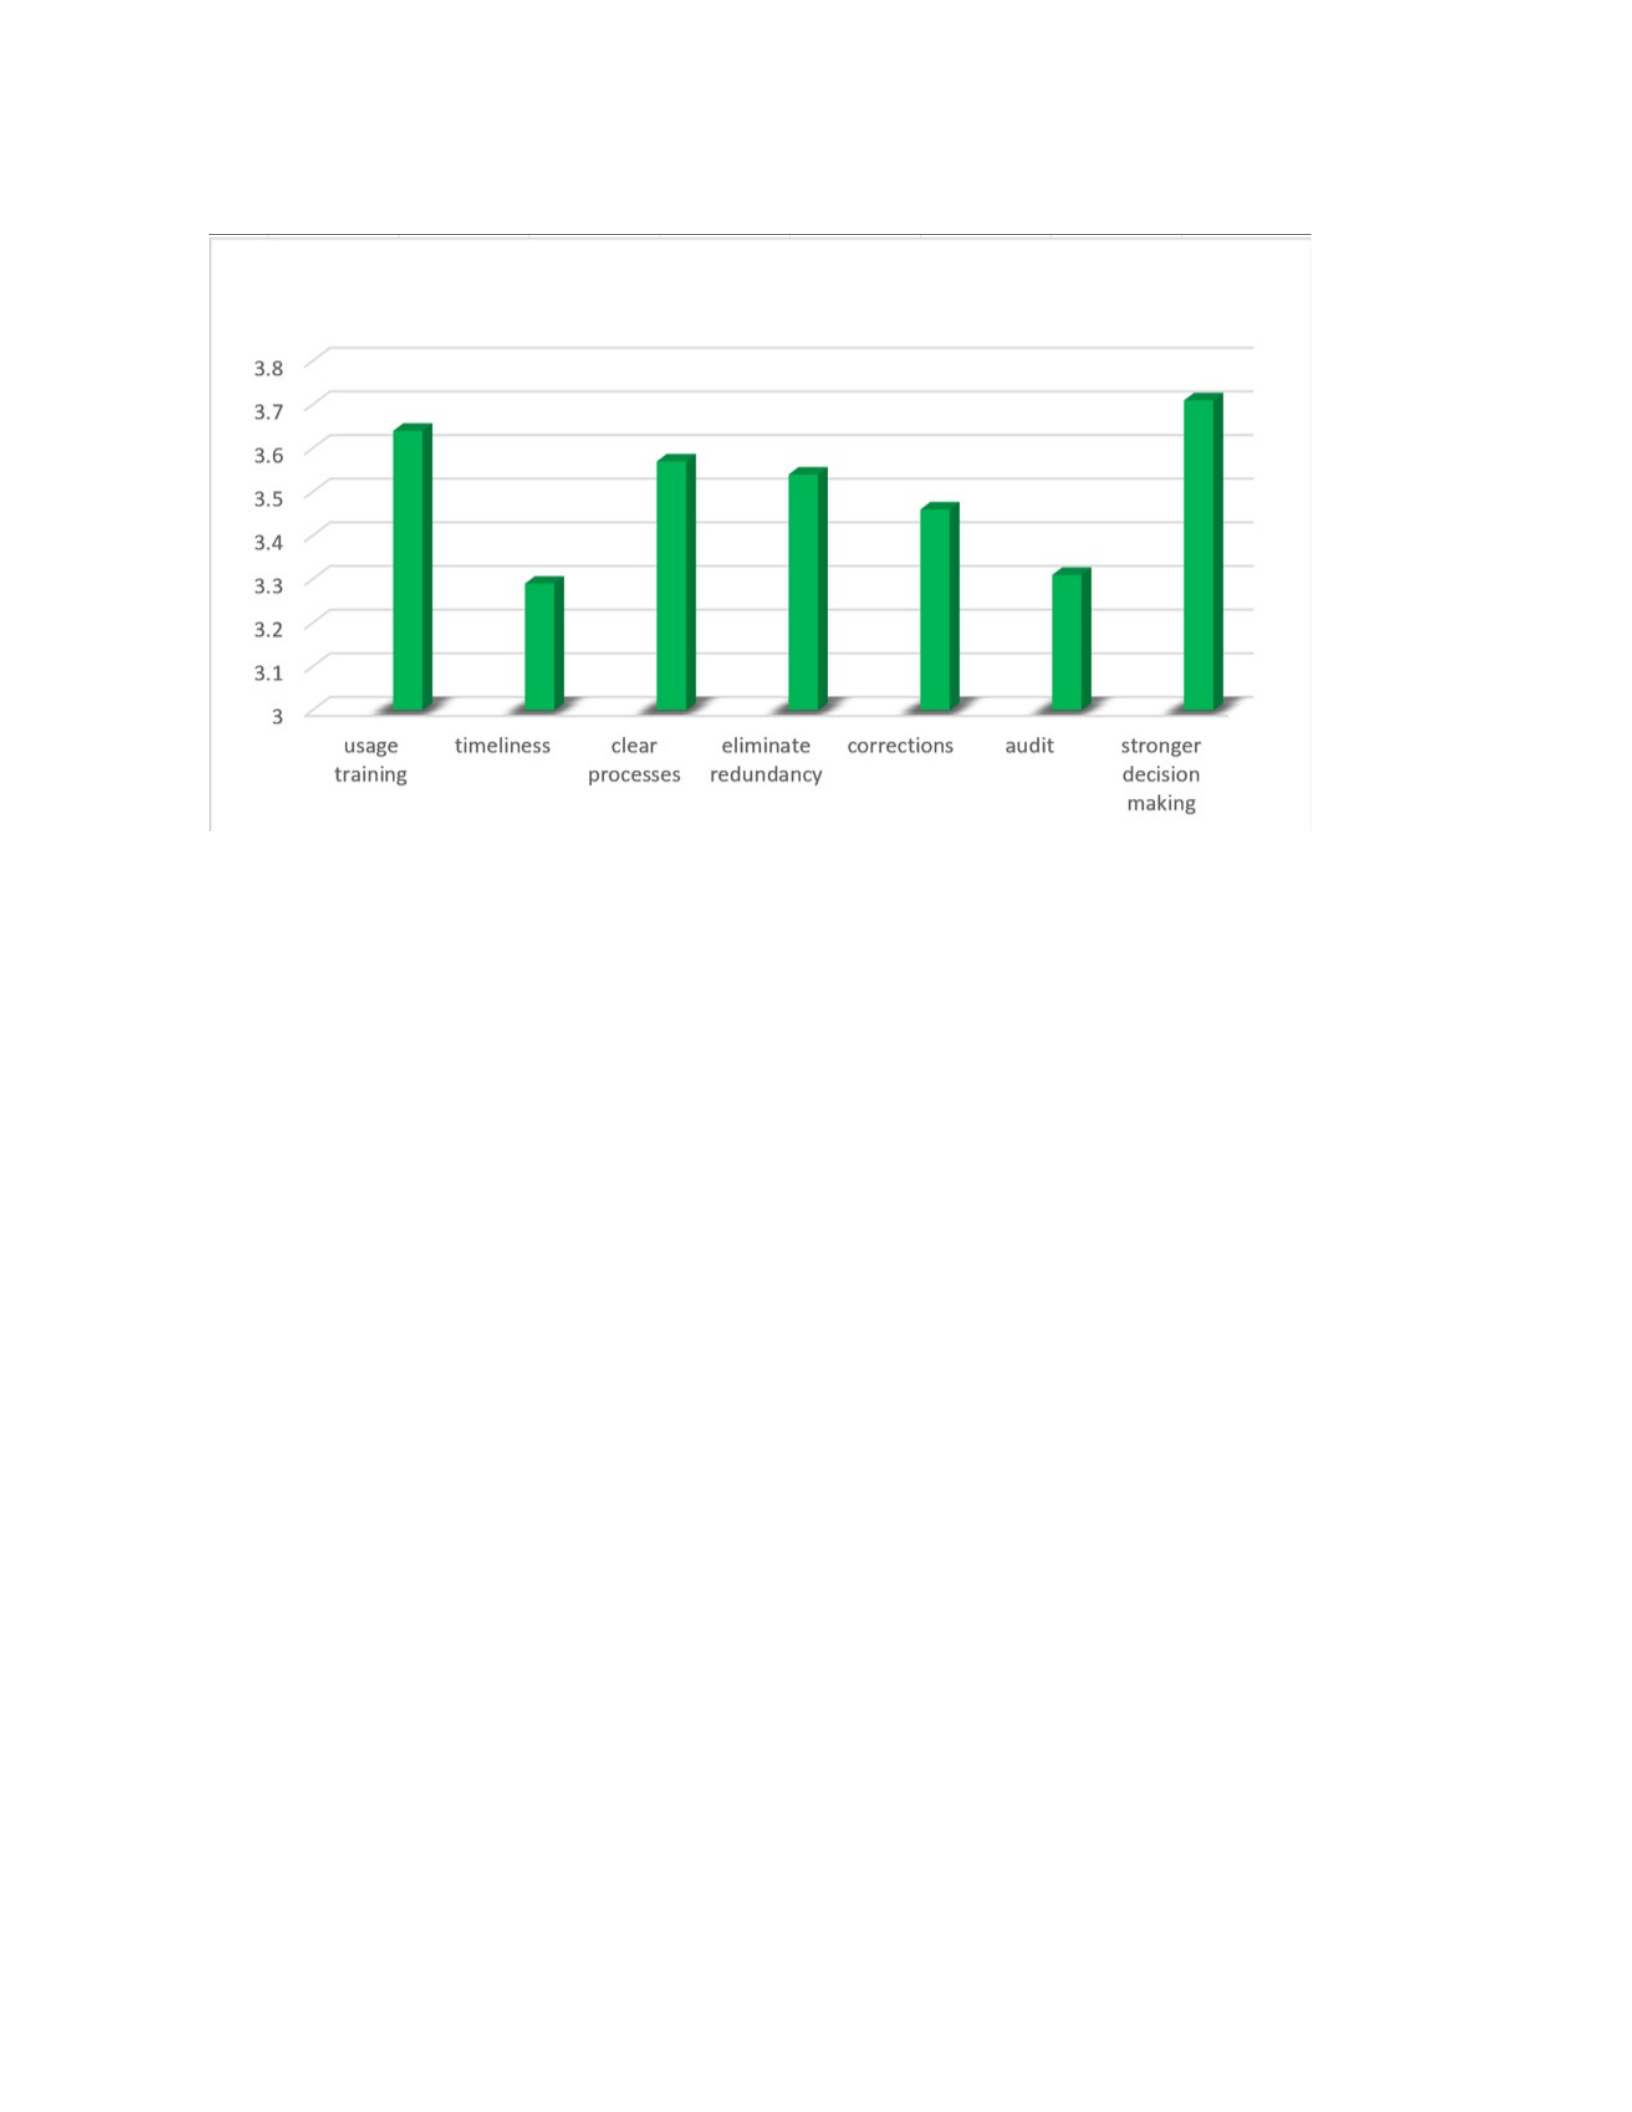
Figure 14. Best practices from Round 3 that ranked high.
Best Practices That Ranked Low
The themes found to rank closest to 1 were: data quality definitions, automated
processes, trustworthy data, integrity, Roles, responsibilities, and ownership, validation,
and metadata. A bar chart of the best practices that ranked lowest in round three can be
found in Figure 15.
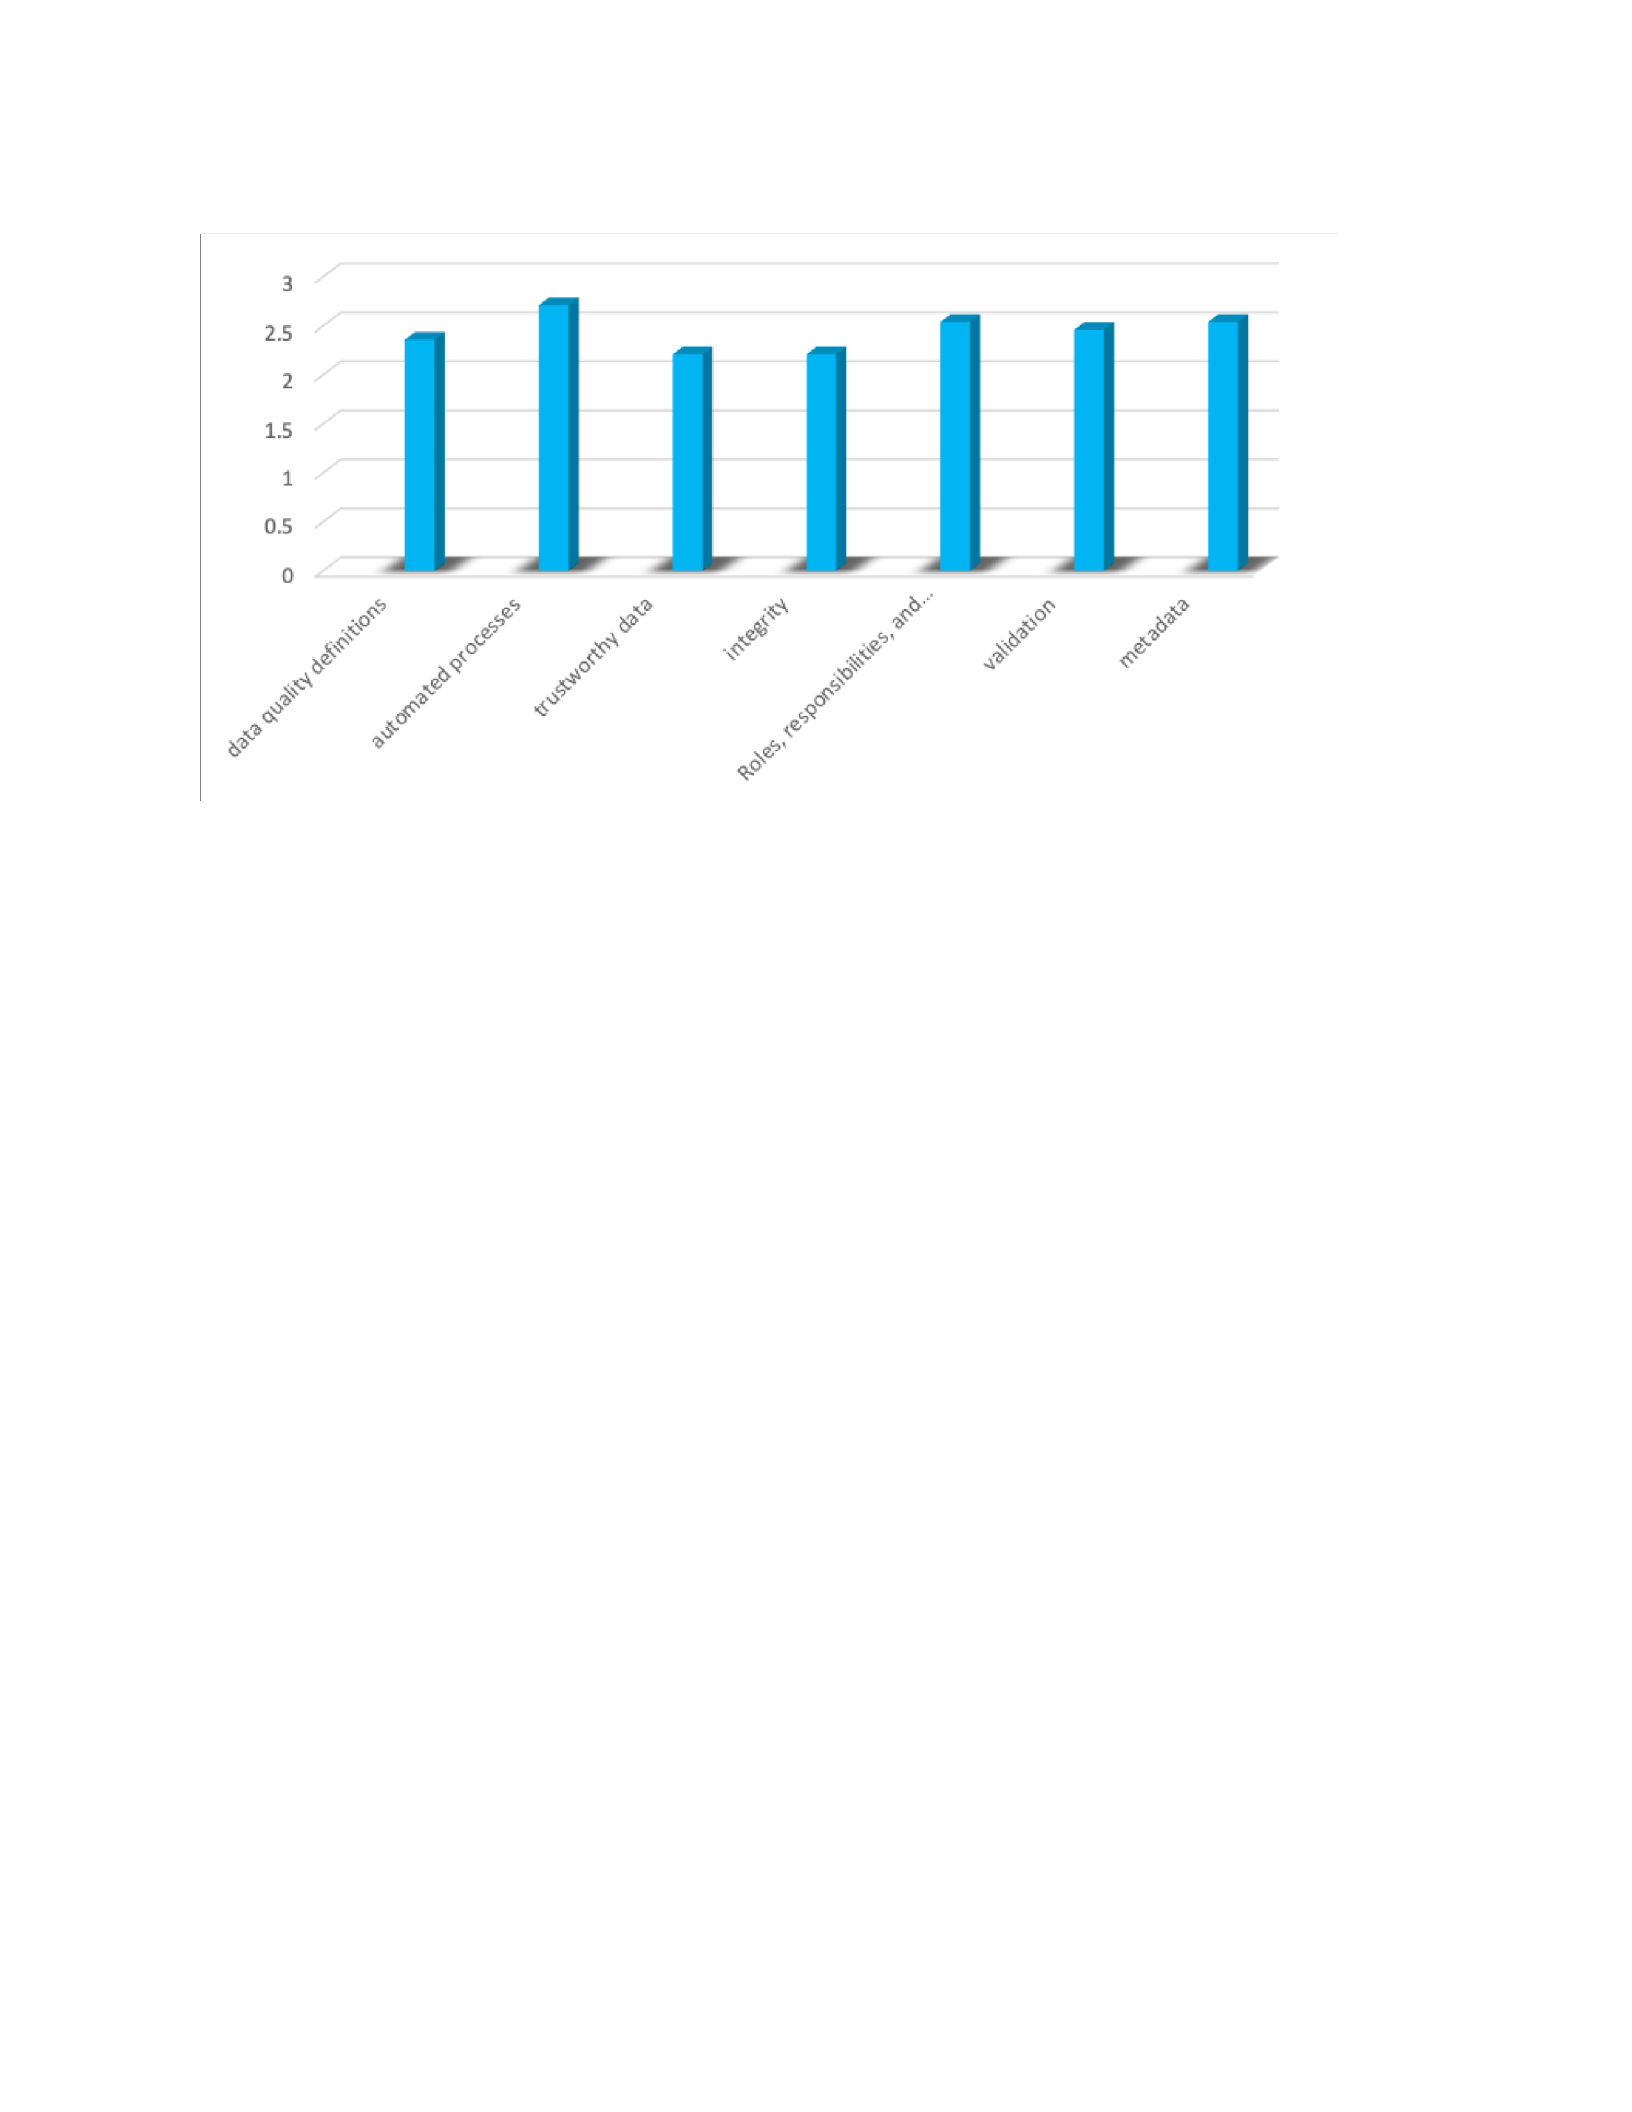
Figure 15. Best practices from round 3 that ranked low.
Comparison of the Best Practices
A view of the best practices side by side to compare how they ranked visually was
necessary to understand how much of a difference the best practices were from one to the
other. For example, although most participants discussed data quality definitions quite a
bit in the beginning, in the end, usage training was found to be more important to best
practices. Participants scored timeliness as a more important best practice against
automated processes. There was a need to have clear processes over trustworthy data. The
two rankings that were the most surprising was the elimination of redundancy over
integrity of the data and audits over validation. Validation was also a common theme in
the beginning. The need for corrections and stronger decision making over
roles/responsibilities and metadata was not surprising. The comparison of the best
practices can be found in Figure 16.
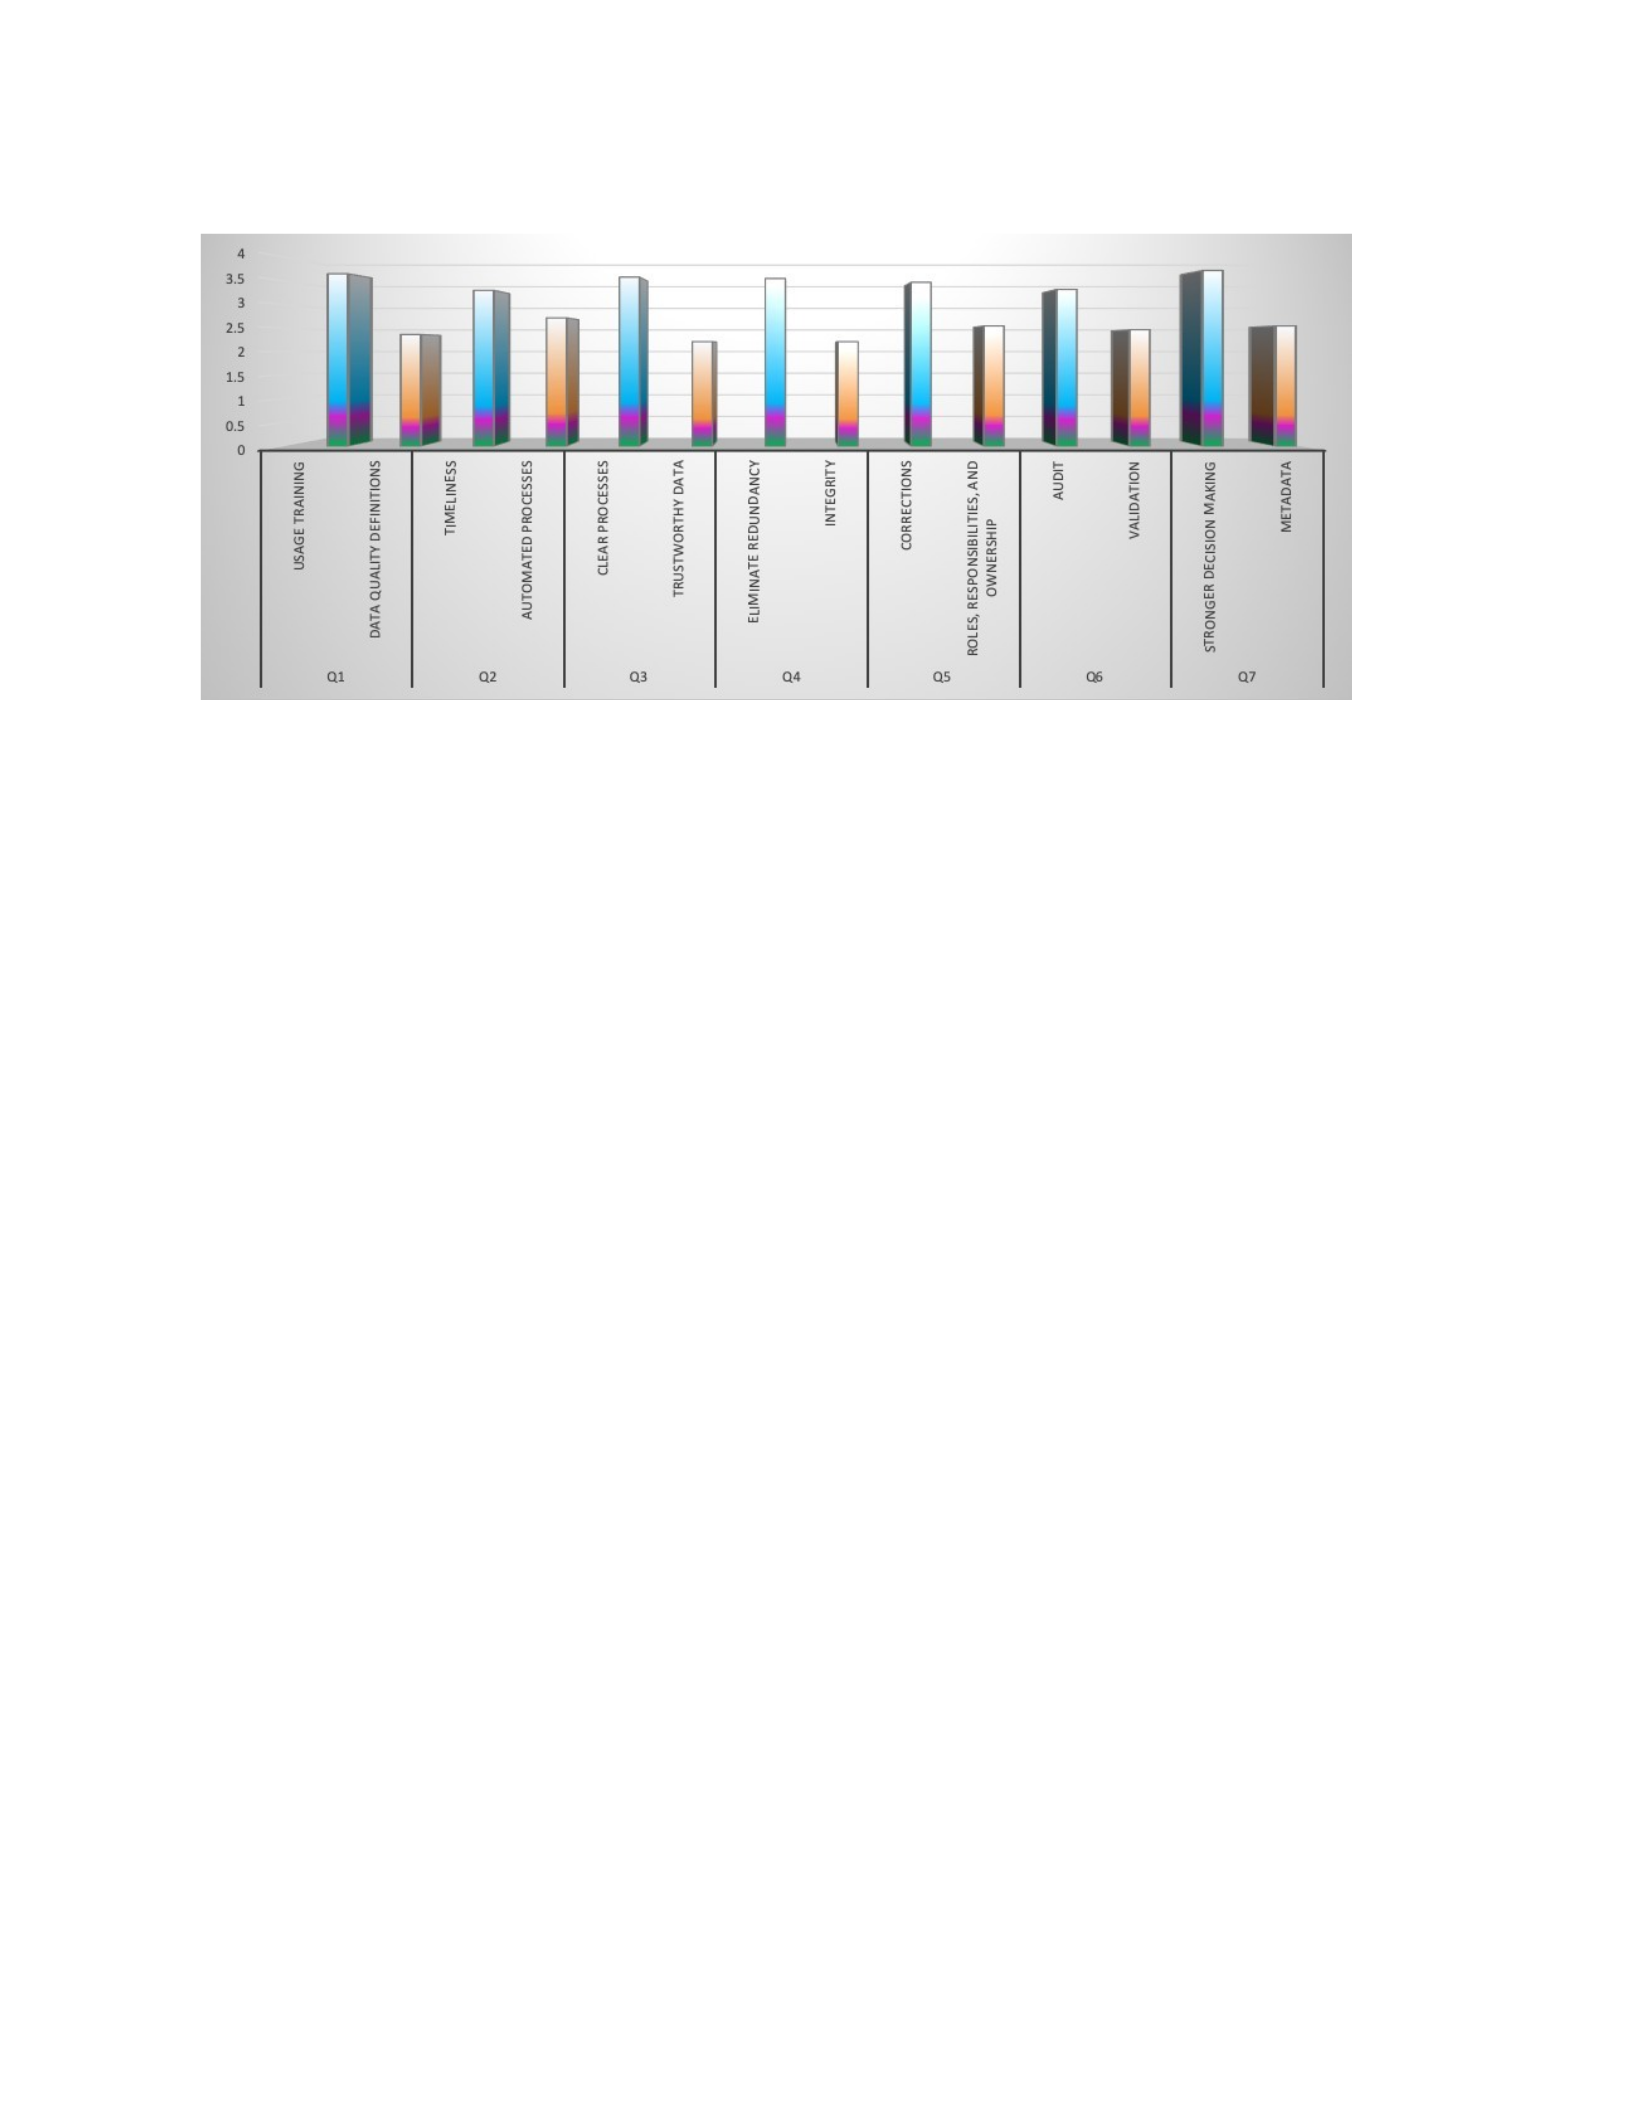
Figure 16. Best practices compared.
Summary
In chapter 4, the following was discussed: filed test, setting, demographics, data
collection, data analysis, and results for all three rounds of my Delphi study. Steps taken
to ensure evidence of trustworthiness was explained. Best practices that ranked high, low
and a comparison of the resulting final best practices was presented and explained. Charts
and diagrams were included for a visual representation of the data collected. In chapter 5,
the interpretation of the findings will be presented as well as the limitations of the study,
implications, and recommendations.
Chapter 5: Discussion, Conclusions, and Recommendations
The purpose of this qualitative Delphi study was to identify best practices for data
quality and data management in healthcare systems. In this study, the best practices
guidelines to include for data quality and data management were further identified. The
best practices in healthcare data quality management and a possible connection to the
findings in the academic fields of management and technology were revealed. The

conceptual framework of Blum and the DQAF were used to guide the structure of the
Delphi survey questions and to identify what information to collect.
The DQAF was used to provide assessment measures based upon data quality
dimensions, and information theory (Blum model) assisted in categorizing the type of
information into each data quality dimension to be assessed. The key findings identified
what the known best practices in the data quality industry were, what best practices
helped to improve data collection in healthcare systems, what the most important best
practices in data quality and integrity were, and what best practices address the secondary
use of data.
Chapter 5 includes interpretation of the findings, limitations of the study,
recommendations, implications, and a conclusion. The interpretation of findings section is
broken down into four subsections to provide more detail.
Interpretation of the Findings
The key findings were grouped into three categories: improvement of data,
secondary data criteria, and data quality and integrity. The best practices identified from
the patterns from the data were turned into professional procedures found to be the most
effective through this research.
Best Practices to Improve Data Collection
Technology is constantly changing. However, the best practices for data integrity
and quality have not changed with the technological advancements. These best practices,
according to current experts in the field, in contrast to former best practices of data

quality definitions, automated processes, roles, responsibilities, and metadata actually
scored very low when assessed for efficacy and effectiveness.
The best practices identified and categorized to improve data collection were user
training and clear processes. Bowman (2013) attributed user error as one of the leading
causes of data quality issues within an EHR. The panelists agreed with researchers such
as Bowman and Weiskopf and Weng (2013) in concluding that training, clear
communication, and cross-checking the data as they move through the process mitigate
errors and provide useful and accurate data. Although cross-checking did not rank high
on the list of best practices, it was discussed earlier in Round 1 as a potential best practice
and should be included to catch any errors. Human error will happen; this was identified
in all of the studies. While human error is inevitable, mechanisms can be put in place to
mitigate these types of data error.
Training, as a best practice, could include such procedures as training focused on
data entry, the purpose of the data, how the data should be handled, and the data checking
processes. Training on clear processes will help the user understand how the data will
flow from one department to another and eventually help in making decisions about
services that can be offered or are necessary for the community. Many end-users who
input the data are unaware of the interrelatedness of multiple systems and how the data
they input are used. This level of transparency could benefit the entire organization by
making the end user accountable for the accuracy and integrity of the data they enter.
Foshay and Kuziemsky (2014) posited that improving data quality should start
with the inclusion of best practices that contain data analytics and quality measures. In as

little as 5 years, experts now consider data analytics and quality measures not as effective
in ensuring data quality improvement. They felt that addressing data quality the endpoint
was less effective. In contrast to the relative importance of data analytics today, analytics
ranked at the bottom of the list of most important best practices by the end of Round 3.
Based on the findings, it appears that experts have shifted towards addressing data
integrity at the point of entry rather than retrospectively at the end of the data flow.
Best Practices That Apply to Secondary Use of Data
The highest-ranking best practices were corrections, audit, and stronger decision-
making matrices in contrast to the accepted best practices focused on trustworthy data and
ownership. Corrections, such as more frequent audits, appeared important and a
significant action item to improve data quality, particularly for using secondary sources
for information. Secondary use of data is common throughout the healthcare industry.
Altwaijry et al. (2013) and Kuehl et al. (2015) advanced the idea that missing
values is a very common data quality issue. Holzinger et al. (2014) contended that
utilization of machines to deal with the massive amounts of data would be ideal and
human observation and audits are critical to ensuring data integrity. This finding suggests
that BI and Artificial Intelligence (AI) may play an increasingly important role in aiding
human data monitoring activities. Kwon et al. (2014) suggested that big data analytics
would enhance decision-making from secondary data. With the advent of Big Data, data
analytics for secondary data is becoming increasingly critical. Missing values could be
addressed and corrected during data integrity audits, using statistical methods to assess
the potential for standard deviation to identify outliers, patterns, and null values. This

approach would then apply business rules to data audits rather than relying solely on
human observation. The application of business rules using software that applies business
rules and AI algorithms would enable a deeper dive into the data than humans can
achieve alone. Complimentary data analytics process with a human interface could more
accurately verify the veracity as well as the strength of the data before they are sent for
decision making.
Mawilmada, Smith, & Sahaman (2012) stated that healthcare services have
suffered because of inaccurate or unusable secondary data. Oracle (2015) reported that
inaccurate secondary data are very costly to the organization, often resulting in missed
opportunities and less than optimum decision making. While neither Mawilmada, Smith,
& Sahama nor Oracle suggested any definitive best practices to ensure the validity of the
secondary data, it is clear that best practices taken must be more robust than those in the
past. This can only happen by combining multiple audit procedures using AI, business
rules, and human assessment.
Best Practices That Apply to Data Quality and Integrity
Dixon et al. (2013) pointed out the best practices they found to be most important
for quality and integrity: accuracy, completeness, consistency, and timeliness. The
topranked best practices are in line with the reported best practices from Dixon et al. This
would mean that the best practices that were considered important in the past in this area
are currently as important within the industry. The current experts concurred in part,
highlighting timeliness and eliminating redundancy. This approach focuses on addressing
data quality and integrity proactively at the onset rather than retrospectively. This shift in

focus aligns with Jerven's (2014) observations that timeliness as is now a critical
dimension of data quality. For example, both Experian (2013) and Hedt-Gauthier et al.
(2012) identified duplicate entries as one of the major data quality errors and flaws.
Redundancy in data can come from improper data entry as well as flawed or outdated
processes, which indicates that synchronization will also become increasingly important
in addressing data quality accuracy and integrity by eliminating redundancy earlier in the
audit process. Without synchronization, the likelihood of duplicate records and database
compromise are virtually certain. Redundancy can have unpredictable cascading effects,
depending on how the data flow to other integrated systems within the network (Cusack
et al., 2013).
Implication and Suggestions for the Future
The consensus among the IT and non-IT healthcare systems data quality
participants identified principle best practices that directed towards timeliness,
eliminating redundancy, on-going rather than retrospective corrections, enhanced audits
combining both human interface audits along with business plan software and possibly
AI, earlier decision making, user training, and the need for clear, transparent data
management processes. Inclusion of these best practice guidelines will enhance existing
accountability measures to reduce the number of digital errors in EHRs, resulting in an
increased likelihood of optimal decisions and quality assurance. Senkubuge et al. (2014)
asserted that there is a need for stakeholders buy in to set in place the policies and take
ownership of the management of their data. Outdated and obsolete best practices should
be abandoned as ineffective and inefficient to address the rapid changes in technology in

favor of current best practices or not included at all. While integrity, validation,
trustworthy data, ownership, data quality definitions, automated processes, roles,
responsibilities, and metadata are still important, how they are addressed and managed
has changed dramatically even within the past decade. Processes and best practices
should be reviewed frequently for currency and monitored, particularly when a significant
software update or new technology for data management is introduced. Data quality and
integrity are key to appropriate patient management and treatment. Best practices that
ensure that quality and integrity are not only essential to the success of the organization
but also to the overall healthcare delivery systems and practices throughout the health
care industry.
Limitations of the Study
One of the major limitations of this study was time. Not all participants who
started in Round 1 completed all three rounds. Time constraints and conditions for
participants were a concern from the beginning of the study because of the commitment
to the 4-month period in 2-week intervals for each round. Some participants were not able
to dedicate the required time to complete the survey for each round as they anticipated
when signing up. There is a possibility that not all factors provided in the study were
considered.
Recommendations
As technology changes, the policies and practices that ensure data quality and
integrity must keep pace. Traditionally, there has been a significant lag between the time
of technology implementation and the evaluation of its effectiveness. Where data

integrity, accuracy, and quality are critical, such as the patient medical record, healthcare
organizations must adopt effective and continuous monitoring practices that address data
quality. Along with those practices, leaders should impanel an in-house panel of experts
that includes all stakeholders from the individual user, IT application specialists, along
with a cross-functional representation of all affected by data flows. There should be an
allowance for modifications and a review for the currency of the best practices in place or
any standardized best practices created as a result of this study.
Implications
Data quality and integrity are integral to the successful operation of any
organization, regardless of the industry. As people and organizations become increasingly
reliant on technology and the massive amounts of data now available, the findings of this
study suggest practices are important to IT and non-IT participants. Service to the
customer and consumer of services and products is dependent on the quality and integrity
of data that the organization's practitioners and leaders use to make decisions, some of
which may be life-altering for a customer. Establishing a list of best practices that are
constantly evaluated for effectiveness would create a logical set of practices that may be
applicable across industries and different healthcare settings.
Conclusion
The quality and integrity of the data begin with policies and practices that start at
the point of user entry or acquisition of secondary data. These policies and practices
should be succinct, comprehensible, uniform, and generalizable. The findings of this
study demonstrate the importance industry experts place on addressing the quality and

integrity of data in the era of Big Data and rapid technological advancement, particularly
with the inclusion of AI that is becoming more ubiquitous in decision-making software.
According to those experts, continual monitoring and audit of not only how data is
collected, used, and managed but also the policies and processes that will ensure the
quality and integrity of that data is essential to overcome the past and current challenges.
In this chapter, an interpretation of the findings was explored. The details were
broken down further with subchapters such as Best Practices to Improve Data Collection,
Best Practices That Apply to Secondary Use of Data, Best Practices That Apply to Data
Quality and Integrity, and What Should be Included as Best Practices. The other major
sections of this chapter were limitations which discussed the issues that occurred beyond
the control of the researcher, recommendations, and implications.

