


1
EXAMINING THE IMPACT OF AFFECT LABELING ON EXPOSURE THERAPY FOR PUBLIC
SPEAKING ANXIETY
Chapter 1 Introduction
Behavioral treatments for anxiety disorders, particularly exposure therapy, are highly
effective in reducing anxiety symptoms (Butler, Chapman, Forman, & Beck, 2006; Hofmann &
Smits, 2008; Tolin, 2010). However, many patients experience limited improvement, drop out of
treatment, or relapse (Loerinc, Meuret, Twohig, Rosenfield, & Craske, submitted for
publication). Exposure therapy, considered the gold standard treatment for anxiety disorders, is
thought to mimic extinction training observed in fear conditioning research. Despite significant
advances in understanding fear extinction in laboratory settings, these findings have not been
widely integrated into clinical practices for treating anxiety disorders.
Given the need for improved treatments, this project aims to bridge the gap between
basic science and intervention research by examining methods to enhance the efficacy of
exposure therapy for public speaking anxiety. Specifically, the study compares the effectiveness
of exposure therapy alone versus exposure combined with affect labeling in reducing anxiety
during public speaking.
Public speaking anxiety is among the most prevalent psychological disorders in the
United States, with estimates ranging from 11% to 30% of the population (Pollard & Henderson,
1988; Stein, Walker, & Forde, 1996; Wittchen, Stein, & Kessler, 1999). For some individuals, it
can be profoundly debilitating, particularly in academic or professional settings where public
presentations are essential. Research indicates that public speaking anxiety correlates with lower
income, reduced educational attainment, and higher unemployment rates (Stein et al., 1996).
Traditional treatments for public speaking anxiety typically combine exposure therapy

2
(e.g., practicing public speaking) with cognitive restructuring, which encourages patients to
reinterpret feared situations neutrally or positively (Heimberg, 2002; Hofmann & Smits, 2008;
Hope, Heimberg, Juster, & Turk, 2000; Rapee & Heimberg, 1997). Recently, affect labeling—
naming one’s emotions in response to a feared stimulus—has emerged as a promising approach
to emotion regulation (Lieberman et al., 2007). Evidence suggests that affect labeling may
enhance the effectiveness of exposure therapy (Kircanski, Lieberman, & Craske, 2012).
Although exposure therapy alone has demonstrated efficacy in treating social anxiety
disorder (Feske & Chambless, 1995), the potential additive benefits of combining it with affect
labeling for public speaking anxiety remain unexplored. This study seeks to address this gap by
evaluating whether affect labeling can augment exposure therapy's effectiveness, ultimately
contributing to improved interventions for individuals with public speaking anxiety.
Fear and Social Anxiety Disorder
The experience of fear is an adaptive mechanism found in many species and helps an
organism respond to threats in the environment. Fear is characterized by autonomic activity,
subjective experience of distress, and behavioral responses. While one of the most common
experiences of fear occurs in the context of threat to the physical self (e.g. possibility of pain or
injury), humans can also experience an anxiety response during social threat (e.g. possibility of
rejection) (Dickerson, Gruenewald, & Kemeny, 2004; Dickerson & Kemeny, 2004). In fact, the
same neural regions activated by physical pain are activated following social rejection
(Eisenberger & Lieberman, 2004). Maintaining social connections with others is one of the
strongest human motivations (Baumeister & Leary, 1995), which suggests that doing so may
have been adaptive for survival in early humans. Rejection by one’s group may have posed a
significant threat to survival in an evolutionary context, and therefore, humans likely evolved

3
mechanisms to avoid being rejected from social groups. Therefore, the experience of anxiety,

4
fear, or shame in situations during which rejection is possible is an adaptive response to social
threat.
For many people, anxiety associated with social threat is excessive and interferes with
the ability to interact with others and perform in social contexts. Anxiety of this magnitude is
diagnosed as social anxiety disorder. Excessive anxiety that occurs only during public speaking
or performance situations is categorized as non-generalized social anxiety and is far more
common than the generalized subtype in which anxiety occurs in multiple social contexts
(Pollard & Henderson, 1988). Speaking in front of an audience is the epitome of social threat
because the attention of the audience is focused solely on the speaker, and there is the possibility
that the audience will dislike or disagree with what the speaker presents. Frequently, those
viewing the speech are peers, colleagues or superiors who may be important to one’s social
network, future career, or educational success. The high prevalence of public speaking fears
may be better understood given the potential for negative evaluation inherent in public speaking.
1.1. Indices of Fear Responding
The defensive motivational system (Masterson & Crawford, 2010) is a system of
behaviors activated in response to environmental threat. Defensive responding includes
autonomic activation, subjective discomfort, and avoidance behavior. The amygdala is a key
region in the experience of and response to threat and has been identified as the mediator
between detection of and response to threat (LeDoux, 2000). In addition, the amygdala plays an
important role in fear learning, memory and extinction (Knight, Smith, Cheng, Stein, &
Helmstetter, 2004; Öhman & Mineka, 2001). Patients with social anxiety disorder show greater
amygdala activity in response to social threat (e.g. angry faces) (Stein, Goldin, Sareen, Zorrilla,

5
& Brown, 2002), as well as non-social negative stimuli (Brühl et al., 2011; Shah, Klumpp,
Angstadt, Nathan, & Phan, 2009).
1.1.1. Autonomic. The experience of threat in the environment activates the sympathetic
nervous system, which prepares the body and mind to respond to threat. Sympathetic activation
is generally thought of as the “fight or flight” response, and includes changes in heart rate (HR)
and sweat gland activity or galvanic skin response (GSR). HR and GSR have been shown to
increase in response to an unconditioned threat stimulus (Deane, 1969) and during public
speaking (Beatty & Behnke, 1991; Myers, 1974); however decreases in HR (fear brachycardia)
also occur in response to threat due to increased attentional focus (Bradley, Codispoti, Cuthbert,
& Lang, 2001). Autonomic activity during laboratory stressors has also been shown to decrease
following treatment for panic disorder (Craske, Lang, Aikins, & Mystkowski, 2005). GSR in
particular is a measure of sympathetic activation as sweat gland activity is stimulated by the
sympathetic nervous system. HR receives input from the sympathetic and parasympathetic
nervous systems, and therefore, while increases in HR indicate sympathetic activity, HR is not a
pure measure of sympathetic nervous system activation (Hugdahl, 1995).
1.1.2. Self report. Fear responding also includes an individual’s subjective response
such as distress and negative cognitions in feared situations. Individuals with social anxiety
report higher levels of anxiety and more negative cognitions during public speaking than non-
anxious controls (Hofmann & DiBartolo, 2000; Levin et al., 1993). In addition, self-reported
anxiety and negative cognitions decrease after completion of treatment (Craske et al., In Press)
and over the course of treatment (Niles, Mesri, Burklund, Lieberman, & Craske, 2013). Given
that subjective experiences of anxiety and distress are one of the primary targets in treatment,
self-report is an essential indicator of fear responding.

6
1.1.3. Behavior. Although physiological and cognitive experiences during threat help an
individual respond appropriately (e.g. fight or flight), anxiety disorders are characterized by
maladaptive avoidance of feared stimuli and situations including escape, retreat, caution or
thought suppression (Craske, 2003). Avoidance can negatively impact work or academic
performance, social relationships, or other important domains, and immediate decreases in
autonomic arousal and subjective discomfort as a result of avoidance reinforce avoidance over
the long term.
1.2. Importance of Enhancing Exposure Effectiveness
One of the key ingredients in treatment for social anxiety disorder is repeated exposure to
feared and avoided social situations (Feske & Chambless, 1995; Rodebaugh, Holaway, &
Heimberg, 2004). Exposure treatment is thought to be analogous to fear extinction in laboratory
studies in which subjects are conditioned to fear a cue that signals the onset of a threatening
stimulus, then subsequently exposed to the cue in the absence of the threat (Bouton, 1993). With
repeated exposure to the cue, subjects show a reduction in fear over time (Watson, 1970).
However, while exposure therapy is highly effective in the treatment of social anxiety
disorder, many patients do not complete treatment, do not benefit from exposure, or show a
return of fear after completion of behavioral treatment (Loerinc et al., Submitted for
Publication). Therefore, there is a need to enhance the effects of exposure with the ultimate
goal of improving treatment outcomes and preventing relapse.
Laboratory studies of fear extinction in animals and humans have also shown a
resurgence of fear after fear has been extinguished (Craske & Mystkowski, 2006; Ricker &
Bouton, 1996). This can occur simply after a period of time (Bouton, Woods, Moody, Sunsay,
& García-Gutiérrez, 2006), after re-experiencing of the feared stimulus or reinstatement

7
(Rescorla & Heth, 1975) and exposure to a different context or renewal (Bouton, 1993). These
phenomena as observed in laboratory studies likely mirror relapse in humans and highlight a
need to find ways of enhancing exposure effectiveness to ultimately reduce relapse rates (Craske
& Mystkowski, 2006).
1.3. Using Language to Enhance Exposure Effectiveness
Although studies of extinction in laboratory animals may simulate exposure for anxiety
disorders, humans have the ability to use language to regulate emotional experiences in ways that
other animals do not. Language is generally used alongside exposure in an attempt to help
patients better understand why the situation is feared and to create more realistic interpretations
of the situation. Although behavioral treatments generally include a cognitive component,
whether this linguistic strategy actually improves the effectiveness of extinction has not been
experimentally assessed in controlled laboratory trials.
Lieberman’s disruption theory of language and emotion (Lieberman, 2003, 2011) posits
that labeling one’s emotional state can disrupt the experience of the emotion. Research in
functional neuroimaging, psychophysiology, and behavior provide evidence that affect labeling
is a promising approach for enhancing emotion regulation during exposure. Linguistic processes
activate areas of the prefrontal cortex, such as the right ventrolateral prefrontal cortex
(RVLPFC) and the medial prefrontal cortex (MPFC), which corresponds to decreases in
activation of limbic emotional response regions such as the amygdala. Activation of the
amygdala in turn affects physiological arousal and subjective experiences of emotion (Kim et al.,
2011), and therefore reductions in amygdala activation should correspond with decreases in
autonomic arousal and subjective experience of distress.

8
Studies of the neural circuitry underlying extinction suggest that the extent to which
prefrontal regions are activated, and the strength of connectivity between prefrontal regions and
the amygdala affect the success of extinction training. Electrical stimulation of the mPFC led to
reduction of conditioned responding after fear conditioning in rats (Milad & Quirk, 2002).
Greater cortical thickness in the mPFC is associated with better extinction effects in humans
(Hartley, Fischl, & Phelps, 2011; Milad et al., 2005), and greater mPFC activity is associated
with better extinction effects of learned US-CS associations (Delgado, Nearing, LeDoux, &
Phelps, 2008; Milad et al., 2005; Phelps, Delgado, Nearing, & LeDoux, 2004). These findings
suggest that down regulation of amygdala activity by mPFC is responsible for successful
extinction. In addition, evidence suggests that patients with social anxiety disorder have weaker
connectivity between the mPFC and the amygdala (Hahn et al., 2011; Kim et al., 2011).
Therefore, treatments that strengthen connectivity between these regions may prove beneficial
in the treatment of social anxiety. The principle of neural plasticity states that repetition of a
process can increase efficiency and efficacy of that process through changes in neuron function,
chemical profile, and structure (Anderson, 2010; Kandel & Schwartz, 1982). Therefore, verbal
processing may enhance connectivity in PFC-Amygdala pathways therefore improving patients’
ability to regulate emotional responses.
1.3.1. Methods of verbalization to activate the RVLPFC. Verbalization such as
cognitive reappraisal is emphasized in treatments for anxiety disorders (Craske, Antony, &
Barlow, 2006; Novalis, Rojcewicz, & Peele, 1993). Reappraisal is a deliberate attempt to reduce
emotional responding by generating neutral or positive (as opposed to negative) interpretations
of a situation. Reappraisal is consistent with cognitive restructuring in cognitive behavioral
therapies for anxiety disorders in which patients are taught to think more flexibly about feared

9
stimuli. Affect labeling, another method of verbalization, is the process of identifying
and labeling emotional experiences (Lieberman, 2011; Pennebaker, 1997), and has been shown
to reduce affective responding to negative stimuli (Lieberman, Inagaki, Tabibnia, & Crockett,
2011). It can be argued that negative thoughts and emotions must first be identified before they
can be modified, so affect labeling is also the first step to cognitive reappraisal (Arch & Craske,
2008). Affect labeling has been categorized as an incidental emotion regulation strategy because
affective change is a consequence of labeling but not an explicit goal (Burklund, Creswell, Irwin,
& Lieberman, 2014). Although both these methods of emotion regulation have been shown to
reduce affective responding to unpleasant stimuli (Lieberman et al., 2011), only one study to
date has examined whether using affect labeling and reappraisal during exposure results in
greater fear reduction at retest compared to exposure alone.
Kircanski, Lieberman & Craske (2012) compared the effects of exposure to a live spider
with and without linguistic processing in spider fearful subjects. Participants were randomly
assigned to use reappraisal or affect labeling during exposure or to complete exposure without
verbalization. At re-test the group that completed exposure with affect-labeling had lower
autonomic activity while viewing a spider and moved closer to the spider compared to the
reappraisal and exposure alone groups. In addition, those who used the greatest number of
anxiety and fear related words during affect labeling showed the greatest reductions in fear
responding. This study provides evidence that affect labeling rather than reappraisal may be a
more promising approach to enhancing the effectiveness of exposure. Therefore, the current
project compared exposure plus affect labeling to exposure alone to specifically test affect
labeling as an augmentation strategy for exposure therapy.

10
1.3.2. Behavioral research on affect labeling. Many studies have demonstrated that
expressing emotions through language is beneficial for psychological wellbeing, physical health,
and cognitive performance. Pennebaker and Beall (1986) were some of the first researchers to
demonstrate through a controlled study that writing about stressful experiences is beneficial for
physical health. Subsequently, hundreds of researchers have assessed the effects of expressive
writing about a wide variety of experiences and within many different populations. Cognitive
processing therapy (Resick & Schnicke, 1993), an effective treatment for post-traumatic stress
disorder, involves systematic written exposure about one’s traumatic experience and the evoked
emotions. Studies that have examined the effect of written or verbal processing of trauma
suggest that linguistic processing of traumatic experiences is beneficial for depression and
anxiety (Hemenover, 2003; Lepore, Silver, Wortman, & Wayment, 1996) and reduces stress
responses to trauma related memories (Smyth, Hockemeyer, & Tulloch, 2008). Studies have also
demonstrated that recording worries about an upcoming exam in writing increases exam
performance (Frattaroli, Thomas, & Lyubomirsky, 2011; Ramirez & Beilock, 2011), and that
writing about negative events decreases intrusive thoughts and increases working memory (Klein
& Boals, 2001). Finally, Lieberman and colleagues (2011) compared participants’ distress while
viewing negative IAPS images with and without affect labeling and found lower reported
distress in the labeling condition despite participants’ predictions that affect labeling would
increase distress.
1.3.3. Neuroimaging and physiological research on affect labeling. Lieberman and
colleagues (2007), demonstrated that when participants label the emotional expression of a face
(e.g. “angry”), they show reduced amygdala activation, and increased activation in the RVLPFC
compared to viewing faces without labeling, or labeling the gender of the face. A significant

11
number of neuroimaging studies have now demonstrated that labeling one’s emotional
experience activates areas of the prefrontal cortex, and reduces activation in the amygdala
(Gorno-Tempini et al., 2001; Hariri, Bookheimer, & Mazziotta, 2000; Hariri, Mattay, Tessitore,
Fera, & Weinberger, 2003; Narumoto et al., 2000). These findings suggest that downregulation
of amygdala activation occurs through projections from prefrontal regions.
Tabibnia and colleagues (2008) examined the effect of repeated exposure to evocative
images with and without negative affective labels. In study 1 in a non-clinical sample, repeated
presentation of emotionally evocative images paired with an affect label resulted in greater
attenuation of GSR upon presentation of the images without a label at 1-week re-test. In study 2,
the effects were replicated in a spider-fearful sample undergoing exposure to images of spiders.
Participants who went through exposure paired with negative labels showed greater attenuation
of GSR at 1-week re-test compared to those who saw no labels or those who saw neutral labels.
1.4. Moderators of Response to Labeling Versus Exposure Alone
Better matching of treatments to individuals can improve therapy outcomes. However,
researchers have yet to identify whether patients who have deficits in a particular skill are more
likely to benefit from treatments that target that skill (deficit model), or whether those who
already gravitate towards a coping approach will benefit most from a treatment that matches that
approach (matching model). Evidence from the expressive writing literature supports both
models with some studies showing that participants high in trait emotional expressivity benefit
most from expressive writing (Austenfeld, Paolo, & Stanton, 2006; Niles, Haltom, Mulvenna,
Lieberman, & Stanton, 2014; Stanton, Kirk, Cameron, & Danoff-Burg, 2000), while others show
that participants with deficits in emotional expression benefit most from expressive writing (Lu
& Stanton, 2009; Páez, Velasco, & González, 1999). The current study will examine whether

12
the matching model can be used to predict who will benefit most from exposure combined with
affect labeling.
1.5. Summary
Fear of public speaking is common and in some cases can cause significant impairment
in functioning. Exposure is an effective treatment method for public speaking anxiety, and is
often combined with cognitive restructuring or other methods of verbalization, but few studies
have examined whether verbalization can enhance the effectiveness of exposure. Evidence from
neuroscience suggests that in anxiety disorders, there are deficits in connectivity between regions
of the prefrontal cortex and the amygdala, which may explain deficits in regulating anxious
responding in these individuals. Affect labeling reduces self-reported distress while viewing
negative images, and when combined with exposure in spider fearful subjects, produces greater
fear attenuation for physiological measures of arousal compared to exposure alone. Affect
labeling activates pathways between prefrontal regions and the amygdala, and therefore,
combining exposure with affect labeling may strengthen prefrontal-amygdala connections
thereby enhancing long-term fear reduction.
1.6. Specific Aims and Hypotheses
The first aim of the study will be to assess whether affect labeling enhances the
effectiveness of exposure compared to exposure alone. We hypothesize that participants who
use affect labeling during exposure will show greater attenuation of fear of public speaking
compared to those who undergo exposure alone. The second aim of the study will be to assess
whether the number of anxiety or fear related words used during exposure predicts greater
attenuation of fear responding at re-test. We hypothesize that participants who use more anxiety
or fear related words compared to other emotion words will show the greatest fear reduction at

13
re-test. The third aim of the study will be to assess whether individual differences in incidental
emotion regulation (i.e. the extent to which affect labeling reduces distress) at baseline moderate
response to exposure with affect labeling versus exposure alone. Consistent with the matching
model, we hypothesize that participants who show strengths in incidental emotion regulation at
baseline will show greater fear attenuation in the labeling condition than in the exposure alone
condition.

14
CHAPTER 2
Method
2.1 Overview of Design, Independent Variables, and Procedure
This study used a 2 (Group) × 3 (Time) mixed design with speech fearful participants.
Groups included an exposure combined with affect labeling condition, and an exposure alone
condition, and Time was three assessment time-points at baseline (Time 1), following exposure
(Time 2) and at one-week follow-up (Time 3). To test Aim 1, the labeling condition was
compared to the exposure alone condition on fear attenuation immediately following exposure
(Time 2) and at one-week follow-up (Time 3). To test Aim 2, the number of anxiety related
emotion words used by participants during exposure was used to predict fear responding
following exposure (Time 2) at one-week follow-up (Time 3). To test Aim 3, incidental emotion
regulation at baseline was examined as a moderator of response to exposure plus affect labeling
versus exposure alone.
For a flowchart of study procedures, see Figure 1. On day one (Time 1), participants first
completed a series of questionnaires followed by a behavioral approach task (BAT-1) during
which autonomic arousal, self-reported affect, cognitions, self-rated performance, and behavioral
avoidance was assessed. Participants next completed an affect labeling task to assess incidental
emotion regulation. Participants were then assigned to the labeling or exposure alone conditions.
Participants were moved to a different room, and completed 10 exposure trials (Exp-1) either
with or without labeling depending on group assignment. Time 2 was three days later, and
participants again underwent 10 exposure trials (Exp-2) with or without labeling depending on
group assignment. After the exposures, participants moved to the room in which the original

15
BAT was conducted, and underwent a second BAT using the same protocol as Time 1 (BAT-2).
Time 3 was eight days later, and participants again completed the BAT using the same method as
at Time 1 and Time 2 (BAT-3).
2.2. Participants
One hundred two participants (AL = 52; Control = 50) were recruited to participate. Two
participants assigned to the control group were not included in analyses. Due to experimenter
error, one participant received the affect labeling exposure protocol rather than the control
protocol on the second day of exposure. The other participant appeared to be answering
randomly on questionnaires and fell asleep during the experiment. Therefore, the final sample
included in analyses was 100. See Figure 2 for a consort diagram of flow through study
procedures. Eligible participants reported a six or higher on anxiety and a five or higher on
avoidance of public speaking on a zero to eight scale (see Appendix A). Participants were
recruited from the UCLA Psychology Subject Pool and using flyers posted around campus.
Participants were given 1 hour of research credit per day of participation or were paid $10.00 per
day if they were not enrolled in a course that required research credit. Participants therefore
received 3 research credits or $30.00 for completing all three days.
Participants were over 18 years of age, fluent in English, free of heart, neurological, or
respiratory conditions, hearing impairment, physician recommendation to avoid stressful
situations, current treatment for public speaking anxiety, or psychotropic medication
prescription for an emotional problem. These participants were excluded due to potential
interference with psychophysiological measurement and for safety precautions.
2.3. Materials

16
A summary of study measures is included in Table 1. Questionnaires are included in Appendix
A.
2.3.1 Indices of fear responding.
2.3.1.1. Physiological activity. Physiological activity recording through the Biopac
system was facilitated using an IBM Pentium II and AcqKnowledge software (AcqKnowledge
4.1 for Windows; BIOPAC Systems, inc). Galvanic skin response (GSR) was recorded from
electrodes attached to the distal phalanges of the second and third finger of a participant’s non-
preferred hand. Heart rate (HR) was recorded from electrodes attached below the right
collarbone and bottom left rib. Physiological data from the final one-minute of the two-minute
baseline (baseline), the one-minute anticipation period prior to the speech (anticipation), and the
one-minute recovery period after completion of the speech (recovery) were analyzed.
All physiological data were first visually inspected to ensure proper measurement. For
HR, one participant at Time 1, and two participants at Time 2 were excluded from analysis due
to recording error. For GSR, nine participants at Time 1, 10 participants at Time 2, and 6
participants at Time 3 were excluded from analysis because no variations in GSR signal were
observed. These numbers are consistent with estimates that approximately 10% (or more in
clinical samples) of individuals do not show a reliable GSR response (Braithwaite, Watson,
Jones, & Rowe, 2013). To assess HR, electrocardiogram signals were collected from two
electrodes, one on the participant’s right clavicle, and one below the bottom left front rib. HR
was defined as the number of heart beats per minute. A band pass filter with a low cutoff of
1.00Hz and a high cutoff of 35.00Hz was applied prior to analysis to limit the effect of signal
noise on the data. GSR was measured using two indices: Skin conductance level (SCL) and
non- specific skin conductance response (SCR-NS). Skin conductance level was defined as the

17
average skin conductance level over each one-minute assessment period and was measured to the
nearest microsiemen (μs). SCR-NS was assessed by calculating the frequency of non-specific
skin conductance responses during each one-minute period. A skin conductance response was
defined by a minimum increase of .02 μs. Data were analyzed using built in analysis tools in
AcqKnowledge software for HR, SCL, and SCR-NS.
2.3.1.2 Personal Report of Public Speaking Anxiety (PRPSA; McCroskey, 1970). See
Appendix A. PRPSA is a 34-item measure that assesses fear of public speaking. Responders
rate their degree of agreement with each statement on a 5-point Likert scale (1=strongly disagree
to 5=strongly agree). The scale has excellent reliability (α=.90) (McCroskey, 1970). Scores of
131 or higher indicate high public speaking anxiety, scores of 98 – 130 indicate moderate
anxiety and scores below 98 indicate low public speaking anxiety. In the current study, α = .97
at Time 1.
2.3.1.3. Subject Units of Distress Scale (SUDS). SUDS is a single item measure used to
assess state anxiety. Participants were shown a 0 to 8 Likert scale with 0 indicating no anxiety
and 8 indicating extreme anxiety. Participants were then asked to report their SUDS ratings at
various points in the study. SUDS ratings were taken directly prior to and following speech
tasks, and when reported, SUDS ratings are the average of the ratings before and after the
speech.
2.3.1.4. Self Statements During Public Speaking (SSPS; Hofmann & DiBartolo, 2000).
See Appendix A. The 10-item SSPS assesses negative and positive cognitions and was
completed immediately after the public speaking task; participants rated the extent to which they
experienced five negative and five positive thoughts during the speaking task. The SSPS shows
good internal consistency (α = .86) and test-retest reliability (r = .80) (Hofmann & DiBartolo,

18
2000). In the current study α = .78 for positive cognitions and .84 for negative cognitions at
Time 1.
2.3.1.5. Optional Speech. At each BAT, participants had the option of speaking on an
additional speech topic. Participants received $5.00 for completing the additional speech.
2.3.2. Other Measures.
2.3.2.1. Performance Rating Form (PRF; Rapee & Lim, 1992). See Appendix A. This
17-item questionnaire assesses self-reported public speaking performance. The scale includes 12
specific items to represent individual behaviors or reactions necessary to good public speaking
(e.g. kept eye contact with audience, had a clear voice), and 5 global items to assess overall
evaluations of performance (e.g. generally spoke well). Participants rate items on a 5-point
Likert scale from 0 (not at all) to 4 (very much) and higher scores indicate better rated
performance. In the current study, α = .91 at Time 1.
2.3.2.2. Patient Health Questionnaire (PHQ; Spitzer, Kroenke, & Williams, 1999). See
Appendix A. The PHQ is a widely used 9-item questionnaire used to assess symptoms of
depression. The PHQ is a valid measure of depressive symptoms (Löwe, Spitzer, et al., 2004)
and is sensitive to change (Löwe, Kroenke, Herzog, & Gräfe, 2004). Patients report the
frequency of experiencing each symptom on a four-point Likert scale. In the current study, α =
.84 at Time 1.
2.3.2.3. Exposure Credibility Questionnaire. See Appendix A. This four-item measure
includes 0-8 Likert scale ratings assessing participants’ perceived credibility of the exposure
task. This measure has been used in previous exposure studies as a potential predictor of study
drop out (Craske, Street, Jayaraman, & Barlow, 1991). In the current study, α = .83 at Time 1.

19
2.3.2.4. Word use during exposure. During exposures, participants assigned to the
verbalization group chose from a set of emotion words displayed on the computer screen using
the keyboard. Their responses were recorded, and the number of anxiety related emotions was
identified for each participant.
2.3.2.5 Mini Social Phobia Inventory (SPIN; Connor, Kobak, Churchill, Katzelnick, &
Davidson, 2001). See Appendix A. This three-item measure assesses symptoms of social
anxiety disorder and is based on a longer 17-item version of the scale. Participants respond to
items on a 0 (not at all) to 4 (extremely) Likert scale. Scores of 6 or higher indicate possible
problems with social anxiety disorder. The scale demonstrates 90% accuracy in identifying a
diagnosis of generalized social anxiety disorder. In the current study α = .86 at Time 1.
2.3.2.6. Mini International Neuropsychiatric Interview (MINI; Lecrubier et al., 1997).
The MINI is a brief fully structured diagnostic interview that can be administered by non-
specialized interviewers. Kappa, specificity, and sensitivity for the MINI compared to diagnoses
obtained on the Composite International Diagnostic Interview are good or very good for all but
three diagnoses (generalized anxiety disorder, agoraphobia, and bulimia), and inter-rater and
test- retest reliability are good (Lecrubier et al., 1997). The current project used only the social
anxiety disorder section of the MINI to determine whether participants met diagnostic criteria for
social anxiety disorder.
2.3.2.7. Incidental Emotion Regulation. Incidental emotion regulation was assessed
using the Affect Labeling Task (Lieberman et al., 2011), which assessed how effective
participants are at decreasing distress using affect labeling. Incidental emotion regulation was
calculated by subtracting participants’ average level of distress when labeling negative images
from their average level of distress when viewing negative images without labeling. Scores

20
ranged from -1.4 to 2.0, and higher incidental emotion regulation scores indicated more
effective emotion regulation. For more details on the Affect Labeling Task, see procedure
below.
2.4. Procedure
Participants who were eligible to participate were scheduled for three appointment times
on days 1, 4 and 9. Appointment times were in the afternoon between 4:00 and 6:00 pm.
Participants were scheduled at the same time on each of the three days. On day 1,
participants completed the Affect Labeling Task, the first BAT (BAT-1), and the first exposure
session (Exp- 1). On day 4, participants completed the second exposure session (Exp-2) and the
second BAT (BAT-2). On day 9, participants completed the third BAT (BAT-3). See Figure 1
for a diagram of study procedures.
2.4.1. Time 1.
2.4.1.1. BAT-1 (30 minutes). On day 1, participants were located in a small room on the
A Level of Franz Hall. When participants arrived, they were consented. After being consented,
participants were interviewed using the Social Anxiety Disorder section of the MINI
Neuropsychiatric Interview by trained research assistants. Following completion of the
interview, electrodes were attached to participants to begin recording by the Biopac
physiological measurement system. Physiological measurement included HR and GSR.
Although physiological activity was recorded throughout the BAT, only measurements taken
during the baseline, anticipation, and recovery periods were analyzed.
Participants then reported on demographic characteristics and completed the PRPSA,
PHQ, and SPIN while acclimating to the environment for approximately 10 minutes. After
completion of the questionnaires, the two-minute baseline period began. Participants were then

21
trained on how to use the SUDS to report anxiety level and practiced entering their SUDS ratings

22
using the computer. The research assistant then provided the participant with instructions for
completing the speech BAT. Once the participant was clear about how the task would proceed, a
one-minute anticipation period began during which the participant sat behind a screen. During
the anticipation period, the three confederates sat in chairs facing the area where the participant
would stand during his/her speech. At the end of the one-minute anticipation, the participant
provided a SUDS rating, and stood in front of the audience. The beginning of the speech task
was signaled by a tone played from the computer, and the first speech topic was displayed on the
computer screen. The participant spoke for one minute on the first topic. The participant then
entered a SUDS rating into the computer and, using the computer, indicated whether or not
she/he was willing to speak on an additional topic for $5.00. If the participant was willing to
continue, a second anticipation period occurred, another SUDS rating was taken, and the next
topic was displayed. After one-minute, a final SUDS rating was taken. Regardless of whether or
not the participant gave the additional speech, a one-minute recovery period followed the final
speech. After completion of the speeches, the participant completed the SSPS, and rated his/her
performance on the PRF. The participant was compensated $5.00 if he/she opted to give the
additional speech.
2.4.1.2. Affect Labeling Task (10 minutes). When the participant was finished speaking,
physiological equipment was removed, and the participant was taken to another location in the
building. The participant then completed a computer task that involved affect labeling and
viewing negative images from the international affective picture system (IAPS; Lang, Bradley, &
Cuthbert, 1999). The Affect Labeling Task followed the procedure of study 1 by Lieberman,
Inagi, Tabibnia, and Crockett (2011). Participants viewed neutral and negative images presented
in two blocks of four images. Each block contained two moderately negative, and two extremely

23
negative images. Prior to each block, participants were prompted by cues that said either
“scene description” (labeling) or “look and let yourself respond naturally” (watching). Pictures
appeared for 5 seconds. For labeling blocks, participants were asked to choose from three labels
that appeared at the bottom of the screen. One label was relevant to the image, and the other two
were not. Two of the labels were negative, and one was neutral. Participants chose a word by
pressing a key on the keyboard that corresponded to the position of the word on the screen. For
watching blocks, participants simply viewed each image for 5 seconds. Following the
presentation of each image, regardless of block condition, participants were asked “How
distressed did you feel while looking at the picture?” and responded on a 9-point Likert scale
with 0 being not distressed, and 8 being very distressed.
2.4.1.3. Exp-1 (30 minutes). The participant was then randomly assigned to complete
exposure alone, or exposure with affect labeling. The participant completed 10 one-minute
repeated exposure speech trials interspersed with 30-second inter-trial intervals between each
exposure. This protocol was chosen based on previous research findings that this duration is
effective in exposure for phobias (Kircanski et al., 2012; Mineka, Mystkowski, Hladek, &
Rodriguez, 1999; Rowe & Craske, 1998). Participants were provided with instructions by a new
experimenter. Once the participant understood the instructions and practiced responding to
questions using the computer, the participant sat behind a folding screen. Three confederates,
including the experimenter, were seated facing the area where the participant gave the speech. A
tone was played from the computer, which signaled to the participant to step in front of the
audience. All participants were prompted by the computer to provide a SUDS rating.
Participants in the affect labeling condition were then prompted by the computer to choose an
emotion and a feared outcome from four options presented on the screen. At the top of the

24
screen, the phrase, “I feel ” was presented followed by three possible emotions and
“other.” All three emotions were negative, and one was always anxiety related (see Appendix B
for list of emotions). The phrase “The audience will ” was then presented followed
by three possible feared outcomes related to the audience’s response to the participant (see
Appendix B for list of feared outcomes). An “other” option was also available. Participants
used the keyboard to respond and had up to 15 seconds to make each selection. Participants
were presented with ten different sets of emotion labels and feared outcomes. Participants in the
exposure alone condition completed shape matching. Participants were first presented with a
large black shape at the top of the screen, then were asked to match the shape with one of three
options at the bottom of the screen. If the shape at the top did not match any of the three shapes
at the bottom, the participants were asked to choose “other.” Participants then did the same
shape matching exercise a second time with blue instead of black shapes. Then, a speech topic
appeared on the screen. Participants spoke for 1 minute then were prompted to step behind the
screen for a 30 second inter-trial interval. The speech exposures were repeated 10 times. After
completion of the exposure, participants completed the ECQ.
2.4.2. Time 2.
2.4.2.1. Exp-2 (30 Minutes). The second exposure session was completed three days
after Exp-1. Two exposure sessions were used to parallel multiple exposures as done in therapy.
Participants received the same instructions as at the previous exposure session. Procedures were
identical to those for Exp-1 on Day 1.
2.4.2.2. BAT-2 (30 Minutes). The second BAT was completed directly following Exp-2.
The protocol for BAT-2 followed the exact protocol for BAT-1, however the speech
topics were different. The same audience that was present for BAT-1 was present for BAT-2.

25
2.4.3. Time 3.
2.4.3.1. BAT-3 (30 minutes). The third and final BAT was completed 8 days after BAT-
1. One-week retest assessed long-term fear reduction and inhibitory learning (Craske et al.,
2008). The protocol for BAT-3 followed the exact protocol for BAT-1 and BAT-2, however the
speech topics were different. The same audience that was present for BAT-1 and BAT-2 was
present for BAT-3.
2.4.4. Speech topics. Speech topics are listed in Appendix C. Across all three BATs,
participants spoke on a total of three to six speech topics depending on how many additional
speeches they were willing to complete. The 6 topics for the BATs were divided into three sets
of two and were counterbalanced across the three time points using a Latin square. Across both
exposure sessions, participants spoke on 20 speech topics. The 20 speech topics for the
exposures sessions were the same across all participants and were administered in the same
order.
2.4.5. Exposure instructions. Copies of exposure instructions are presented in Appendix
D. All participants received the same set of instructions to keep research assistants blind to
condition. Participants were informed that they would be giving 10 speeches in front of a small
audience and that they may be asked to label the emotion that they were feeling. They were
asked to choose the emotion from a list of four emotions that best matched how they were
feeling at that moment. They were encouraged to choose one of the emotions listed, but if they
really felt that the words did not match their experience, they were allowed to choose “other.”
They were also instructed that they may be asked to choose how they thought the audience
might respond to them while they were speaking, and were asked to choose an outcome from the
list that best matched their expectation of how the audience would respond. They were again

26
encouraged to choose one of the options listed, but could also select other. Finally, they were
informed that they may be asked to match shapes, and were asked to choose the shape from a list
of four possible shapes that matched a large target shape at the top of the screen. If none of the
shapes listed matched the target shape, they were instructed to choose other. Finally, they were
informed that they might see the same shaping matching screen with blue instead of black
shapes.
2.5. Data Analysis
Analyses were conducted using Stata 12. Dependent measures assessed for all three study
aims were HR, SCL, SCR-NS, PRPSA, SUDS, SSPS, PRF, and optional speech. For analyses
including HR, HR2 at baseline was used as a covariate in the models to account for the non-
linear relationship between heart rate and activity in the sympathetic and parasympathetic
nervous systems (Cacioppo, Tassinary, & Berntson, 2007). SCL was log transformed in
accordance with recommendations by Venables and Christie (as cited in Cacioppo et al., 2007).
For models including SCR-NS (a count variable) as the dependent measure, Poisson regression
was used to account for non-normality. For models including optional speech (a dichotomous
variable) as the dependent variable, logistic regression was used. For analyses of the recovery
period (following participants’ decision to complete or avoid the optional speech), optional
speech was tested as a covariate and included in the model when significant. All tests were two-
tailed with an α level of .05.
All three study aims were tested using multi-level modeling (MLM) because
measurement was repeated at three time-points for each participant. MLM accounts for within
and between participant variance. In addition, MLM effectively handles missing data by
including all participants in the model regardless of missing data points. Time was modeled at

27
level 1, and participant level variables (e.g. Group) were modeled at level two. Time was
modeled using two segments. Once segment modeled change from Time 1 to Time 2, and the
second modeled change from Time 2 to Time 3. This approach was chosen based on a pattern of
results typically observed in intervention studies characterized by an initial steep change in
symptoms from pre to post intervention and a leveling off of change through follow-up. For
each dependent variable, random effects of the intercept and slope and their covariance were
first included in the model. Non-significant random effects (tested using likelihood ratio tests)
were removed from the model. For each dependent variable, the model with the fewest random
effect parameters necessary to achieve optimal model fit was chosen.
For Aim 1, predictors in the model were Time, Group and the Time × Group interaction,
and the Time × Group fixed effect was examined for significance. For Aim 2, predictors in the
model were Time, number of anxiety labels chosen, and the Time × number of anxiety labels
interaction, and the Time × number of anxiety labels fixed effect was examined for significance.
Analyses for aim 2 were only conducted within the AL group. For Aim 3, predictors in the
model were Time, Group, incidental emotion regulation, Time × Group, Time × incidental
emotion regulation, Group × incidental emotion regulation, and Time × Group × incidental
emotion regulation, and the Time × Group × incidental emotion regulation fixed effect was
examined for significance. If the three way interaction (test of moderation) was not significant,
it was dropped from the model and the Time × incidental emotion regulation (test of prediction)
fixed effect was examined for significance.
2.6. Effect Size
For study Aim 1, effect sizes reported are Cohen’s d, and were calculated using an
approach described by Feingold (2009) for estimating group differences in randomized clinical

28
trials with repeated measures. For study Aims 2 and 3, effect sizes reported are Cohen’s f2 and
were estimated using an approach outlined by Selya and colleagues (2012). Cohen’s f2 uses
residual variance from the model to estimate effect size. However, for multi-level models, effect
sizes calculated using residual variance and proportion of variance explained should be
interpreted with caution because the addition of variables to the model can, in some cases,
increase residual variance resulting in negative estimates of explained variance and even of
effect size (Snijders & Bosker, 1994) In addition, this method cannot be used for non-
continuous dependent measures. As a result, effect sizes are not reported for analyses with
SCR- NS (count variable) or optional speech (dichotomous variable) as the outcome.
2.7. Missing Data
There were missing data on a number of demographic, predictor, and dependent
measures. Reasons for missing data included participant non-response, experimenter error,
inadvertent deletion, and computer program failure. The numbers of missing data points for all
study variables are shown in Table 2.
2.8. Power Analyses
Effect sizes for group comparisons in the study by Kircanski and colleagues (2012), in
which verbalization during exposure was compared to exposure alone in spider phobic
participants, ranged from .58 to .99 depending on which outcome measure was assessed. To
achieve power of 0.8, for an effect size of .60, the goal sample size was 72 participants.

29
CHAPTER 3
Results
3.1. Preliminary Analyses
3.1.1. Sample characteristics. Groups did not significantly differ on any demographic
or clinical characteristics at baseline (ps > .05). Table 3 includes baseline descriptive statistics
and statistical tests for group differences. At baseline, 54% of the sample fell in the “high”
public speaking anxiety range on the PRPSA (scores above 131), 46% of the sample fell in the
moderate range (scores between 97 and 131), and 0% of the sample fell in the “low” public
speaking anxiety range. The current sample had a mean PRPSA score of 133.0, which is
approximately one standard deviation above the mean of 114.6 (SD = 17.2) observed in a college
sample (McCroskey, 1970). On the mini-SPIN, 65% of the sample fell at or above the clinical
cut-off of 6, indicating possible problems with social anxiety, and 36% met criteria for social
anxiety disorder based on the MINI diagnostic interview. On the PHQ, 49% of the sample fell in
the minimal range, 39% in the mild range, 7% in the moderate range, 4% in the moderately
severe range, and 1% in the severe range for depressive symptoms.
3.1.2. Descriptive statistics and correlations among study variables. Table 4 includes
raw means and standard deviations for all dependent measures at all three time points by group.
Table 5 includes proportions of affect labels and feared outcomes chosen at Exp1 and Exp2 (AL
group only), mean SUDS ratings at the beginning and end of Exp1 and Exp2 by group, and
ECQ ratings at Exp1 by group. Table 6 includes correlations among dependent measures, affect
labeling variables collected during exposure, and incidental emotion regulation.

30
3.1.3. Comparison of completers vs. dropout. Table 7 includes means and standard
deviations for dependent measures and exposure variables for completers and participants who
dropped from the study as well as statistical tests comparing the two groups. Participants who
dropped reported significantly fewer positive self statements during the public speaking task,
rated their performance significantly lower, had significantly higher HR during anticipation of
giving a speech, had marginally significantly higher HR when recovering after giving a speech,
had marginally significantly higher SCR-NS during anticipation of giving a speech, and were
marginally significantly less likely to give the optional speech compared to participants who
completed the study. Dropout did not differ between the AL group (N=11) and the Control
group (N=8) χ2 = .33, p = .568. Given that significant differences were found between
completers and those who dropped from the study, dropout was tested as a covariate in each
model, and when significant, was included in the final model.
3.2. Primary Analyses Aim 1. Does Affect Labeling Enhance Exposure Effectiveness
Compared to Exposure Alone?
Figures are provided for each dependent variable assessed. For each model tested,
interaction effects from Time 1 to Time 2, Time 2 to Time 3, and Time 1 to Time 3 are reported.
For significant and marginally significant interactions, the following simple effects are tested.
(1) Group differences at Time points 2 and 3; (2) Simple slopes (whether slopes differ
from zero) from Time 1 to Time 2, Time 2 to Time 3, and/or Time 1 to Time 3 (depending on
significant interactions).
3.2.1. Heart rate.

31
3.2.1.1. Anticipation. Results are displayed in Figure 3. For HR during anticipation of
giving a speech, the Time × Group interactions from Time 1 to Time 2 (p = .934), Time 2 to
Time 3 (p = .191), and from Time 1 to Time 3 (p = .152) were not significant.
3.2.1.2. Recovery. Results are displayed in Figure 4. For HR during recovery following
the speech, the Time × Group interactions from Time 1 to Time 2 (p = .654) and from Time 1 to
Time 3 (p = .153) were not significant. The Time × Group interaction from Time 2 to Time 3
was significant (b = -3.79, 95% Confidence Interval (CI) = -7.4 to -.2, p = .041, d = .33) such
that participants in the AL group showed a steeper decrease in HR from Time 2 to Time 3 than
did participants in the Control group. Tests of group differences revealed no significant
differences at Time 2 (p =.419) or at Time 3 (.281). Tests of simple slopes from Time 2 to Time
3 revealed a significant increase in HR in the Control group (change = 2.77, p = .036) and no
significant change in the AL group (p = .432).
3.2.2. Skin conductance level.
3.2.2.1. Anticipation. Results are displayed in Figure 5. For SCL during anticipation of
giving a speech, the Time × Group interactions from Time 1 to Time 2 (p = .690), Time 2 to
Time 3 (p = .947), and Time 1 to Time 3 (p = .743) were not significant.
3.2.2.2. Recovery. Results are displayed in Figure 6. For SCL during recovery following
the speech, the Time × Group interactions from Time 1 to Time 2 (p = .302), Time 2 to Time 3
(p = .861), and Time 1 to Time 3 (p = .227) were not significant.
3.2.3. Non-specific skin conductance response.
3.2.3.1. Anticipation. Results are displayed in Figure 7. For SCR-NS during anticipation
of giving a speech, the Time × Group interactions from Time 1 to Time 2 (p = .875), Time 2 to
Time 3 (p = .778), and Time 1 to Time 3 (p = .878) were not significant.

32
3.2.3.2. Recovery. Results are displayed in Figure 8. For SCR-NS during recovery
following the speech, the Time × Group interaction from Time 1 to Time 2 was not significant (p
= .587), whereas the interactions from Time 2 to Time 3 (b = -1.14, CI = -2.1 to -.2, p =
.023, d = 1.0) and Time 1 to Time 3 (b = -.90, CI = -1.8 to 0, p = .023, d = .79) were significant
such that participants in the AL group showed a steeper decrease in SCR-NS from Time 2 to
Time 3 and from Time 1 to Time 3 than did participants in the Control group. Tests of group
differences revealed no significant group difference at Time 2 (p =.273) and a marginally
significant difference at Time 3 (difference = .29, p = .100) such that participants in the AL
group had fewer SCR-NS during recovery than did participants in the Control group. Tests of
simple slopes from Time 2 to Time 3 revealed a marginally significant reduction in SCR-NS
during recovery in the AL group (change = -.61, p = .077), but not in the Control group (p
= .146), and no significant changes from Time 1 to Time 3 in either group (ps > .123).
3.2.4. Personal Report of Public Speaking Anxiety. Results are displayed in Figure 9.
For PRPSA, the Time × Group interactions from Time 1 to Time 2 (p = .196), Time 2 to
Time 3 (p = .875), and Time 1 to Time 3 (p = .394) were not significant.
3.2.5. Subjective Units of Distress. Results are displayed in Figure 10. For SUDS, the
Time × Group interactions from Time 1 to Time 2 (p = .385), Time 2 to Time 3 (p = .328),
and Time 1 to Time 3 (p = .901) were not significant.
3.2.6. Self Statements During Public Speaking.
3.2.6.1. Positive. Results are displayed in Figure 11A (higher scores indicate more
positive cognitions). For SSPS Positive, the Time × Group interactions from Time 1 to Time 2
(p = .837), Time 2 to Time 3 (p = .264), and Time 1 to Time 3 (p = .316) were not significant.

33
3.2.6.2. Negative. Results are displayed in Figure 11B. For SSPS Negative, the Time ×
Group interactions from Time 1 to Time 2 (p = .952), Time 2 to Time 3 (p = .320), and Time 1
to Time 3 (p = .417) were not significant.
3.2.7. Performance Rating Form. Results are displayed in Figure 13 (higher scores
indicate better self-rated performance). For PRF, the Time × Group interactions from Time 1 to
Time 2 (p = .544) and from Time 1 to Time 3 (p = .353) were not significant whereas, the
interaction from Time 2 to Time 3 was marginally significant (b = -3.06, CI = -6.5 to .34, p =
.077, d = .36) such that participants in the Control group showed a steeper increase in
PRF from Time 2 to Time 3 than did participants in the AL group. Tests of group differences
revealed no significant differences at Time 2 or Time 3 (ps > .210). Tests of simple slopes
revealed a significant increase from Time 2 to Time 3 in PRF in the Control group (change =
4.57, p <
.001), but not in the AL group (p = .217).
3.2.8. Optional speech. Results are displayed in Figure 12. For optional speech, the
model did not converge when all three time points were included. Therefore, the model was run
including Time 1 and Time 3 only. The Time × Group interaction from Time 1 to Time 3 was
not significant (p = .669).
3.3. Secondary Analyses Aim 1. Does Affect Labeling Enhance Exposure Effectiveness for
High Labelers Compared to Exposure Alone?
A number of participants assigned to the affect labeling condition chose no or very few
anxiety labels; we evaluated whether participants who more consistently selected anxiety labels
during exposures showed greater fear reduction compared to those assigned to exposure alone.
Participants were categorized into “low” or “high” labelers based on the median frequency of

34
affect labels chosen, and the high labelers were compared to participants in the control condition.

35
3.3.1. Heart Rate.
3.3.1.1. Anticipation. Results are displayed in Figure 14. For HR during anticipation of
giving a speech, the Time × Group interactions from Time 1 to Time 2 (p = .554) and Time 1 to
Time 3 (p = .198) were not significant whereas the interaction from Time 2 to Time 3 was
marginally significant (b = -4.96, CI = -10.3 to .4, p = .071, d = .39) such that participants in the
AL group showed a steeper decrease in HR from Time 2 to Time 3 than did participants in the
Control group. Tests of group differences revealed no significant differences at Time 2 or Time
3 (ps > .174). Tests of simple slopes from Time 2 to Time 3 revealed no significant change in
either group (ps > .191).
3.3.1.2. Recovery. Results are displayed in Figure 15. For HR during recovery following
the speech, the Time × Group interaction from Time 1 to Time 2 was not significant (p = .328).
The interaction from Time 2 to Time 3 (b = -6.47, CI = -10.6 to -2.3, p = .002, Cohen’s d = .56)
was significant and the interaction from Time 1 to Time 3 was marginally significant (b = -4.39,
CI = -8.9 to .1, p = .054, Cohen’s d = .38) such that high labelers in the AL group had a steeper
decline in HR during recovery than did participants in the Control group. Tests of group
differences revealed no group differences at Time 2 or Time 3 (ps > .129). Tests of simple
slopes from Time 1 to Time 3 revealed a marginally significant increase in HR in the Control
group (change = 2.63, p = .057) and no significant change in the AL group (p = .333). Tests of
simple slopes from Time 2 to Time 3 revealed a significant increase in HR in the Control group
(change = 2.70, p = .033) and a significant decrease in HR in the AL group (change = -3.77, p =
.027).
3.3.2. Skin conductance level.

36
3.3.2.1. Anticipation. For SCL during anticipation of giving a speech, the Time × Group
interactions from Time 1 to Time 2 (p = .281), Time 2 to Time 3 (p = .921) and Time 1 to Time
3 (p = .329) were not significant.
3.3.2.2. Recovery. For SCL during recovery following the speech, the Time × Group
interactions from Time 1 to Time 2 (p = .603), Time 2 to Time 3 (p = .676), and Time 1 to
Time 3 (p = .339) were not significant.
3.3.3. Non-specific skin conductance response.
3.3.3.1. Anticipation. Results are displayed in Figure 16. For SCR-NS during
anticipation of giving a speech, the Time × Group interactions from Time 1 to Time 2 (p = .715)
and Time 2 to Time 3 (p = .128) were not significant. The interaction from Time 1 to Time 3
was significant (b = -.62, CI = -1.2 to 0, p = .049, d = .35) such that high labelers in the AL
group had a steeper decline in SCR-NS during anticipation than did participants in the Control
condition. Tests of group differences revealed no group difference at Time 2 (p = .287), and a
significant group difference at Time 3 (difference = -.89, p = .008) such that the AL group had
fewer SCR-NS than did the Control group. Tests of simple slopes revealed a marginally
significant decrease in SCR-NS from Time 1 to Time 3 in the Control group (p = .055), and a
significant decrease in SCR-NS from Time 1 to Time 3 in the AL group (change = -.93, p =
.001).
3.3.3.2. Recovery. Results are displayed in Figure 17. For SCR-NS during recovery
following the speech, the Time × Group interaction from Time 1 to Time 2 was not significant (p
= .385). The interaction from Time 2 to Time 3 (b = -1.87, CI = -3.3 to -.4, p = .013, d = 1.63)
was significant, and the interaction from Time 1 to Time 3 was marginally significant (b = -.14,
CI = -2.8 to 0, p = .055, Cohen’s d = 1.21) such that high labelers in the AL group had a steeper

37
decline in SCR-NS during recovery than did participants in the Control group. Tests of group
differences revealed no significant group difference at Time 2 (p = .536), and a significant group
difference at Time 3 (difference = .47, p = .008) such that the AL group had fewer SCR-NS
during recovery than did the Control group. Tests of simple slopes from Time 2 to Time 3
revealed a significant decrease in SCR-NS during recovery in the AL group (change = -1.33, p =
.041), but not in the Control group (p = .143), and no significant change from Time 1 to Time 3
in either group (ps > .131).
3.3.4. Personal Report of Public Speaking Anxiety. Results are displayed in Figure 18.
For PRPSA, the Time × Group interactions from Time 2 to Time 3 (p = .957) and Time 1 to
Time 3 (p = .214) were not significant. The interaction from Time 1 to Time 2 was marginally
significant (b = 5.37, CI = -.9 to 11.7, p = .095, d = .35) such that participants in the Control
group had a steeper decline in PRPSA than did high labelers in the AL group. Tests of group
differences revealed no significant group difference at Time 2 (p = .122) or Time 3 (p = .184).
Tests of simple slopes revealed a significant decrease in PRPSA from Time 1 to Time 2 in the
AL group (change = -5.33, p = .041) and in the Control group (change = -10.70, p < .001).
3.3.5. Subjective Units of Distress. Results are displayed in Figure 19. For SUDS, the
Time × Group interactions from Time 2 to Time 3 (p = .692) and Time 1 to Time 3 (p = .209)
were not significant. The interaction from Time 1 to Time 2 was marginally significant (b = .57,
CI = -.1 to 1.2, p = .079, d = .38) such that participants in the Control group showed a steeper
decrease in SUDS from Time 1 to Time 2 than did participants in the AL group. Tests of group
differences revealed a significant group difference at Time 2 (difference = .81, p = .038) such
that the AL group had higher SUDS ratings than did the Control group. Groups did not
significantly differ at Time 3 (p = .104). Tests of simple slopes revealed a significant decrease in

38
SUDS from Time 1 to Time 2 in the AL group (change = -.70, p = .007) and in the
Control group (change = -1.28, p < .001).
3.3.6. Self Statements During Public Speaking.
3.3.6.1. Positive. For SSPS positive, the Time × Group interactions from Time 1 to Time
2 (p = .908), Time 2 to Time 3 (p = .240), and Time 1 to Time 3 (p = .418) were not significant.
3.3.6.1. Negative. For SSPS negative, the Time × Group interactions from Time 1 to
Time 2 (p = .853), Time 2 to Time 3 (p = .212), and Time 1 to Time 3 (p = .268) were not
significant.
3.3.7. Performance Rating Form. For PRF, the Time × Group interactions from Time 1
to Time 2 (p = .841), Time 2 to Time 3 (p = .143), and Time 1 to Time 3 (p = .177) were not
significant.
3.3.8. Optional Speech. For the optional speech, the Time × Group interaction from
Time 1 to Time 3 was not significant (p = .649).
3.4. Aim 2. Does the Number of Anxiety Related Labels Used During Exposure Predict
Greater Attenuation of Fear Responding at Re-Test?
For each model tested, the significance of the Time × Number of Anxiety Labels
interaction from Time 1 to Time 2, Time 2 to Time 3, and Time 1 to Time 3 are reported. For
significant and marginally significant interactions, tests of whether participants at one standard
deviation below the mean (-1SD) on Number of Anxiety Labels differ from those at one standard
deviation above the mean (+1SD) at Time points 1, 2 and 3.
3.4.1. Heart rate.

39
3.4.1.1. Anticipation. For HR during anticipation of giving a speech, the Time × number
of anxiety labels interactions from Time 1 to Time 2 (p = .525), Time 2 to Time 3 (p = .387), and
Time 1 to Time 3 (p = 783) were not significant.
3.4.1.2. Recovery. For HR during recovery following the speech, the Time × number of
anxiety labels interactions from Time 1 to Time 2 (p = .695), Time 2 to Time 3 (p = .325), and
Time 1 to Time 3 (p = .517) were not significant.
3.4.2. Skin conductance level.
3.4.2.1. Anticipation. For SCL during anticipation of giving a speech, the Time × number
of anxiety labels interactions from Time 1 to Time 2 (p = .307), Time 2 to Time 3 (p = .878), and
Time 1 to Time 3 (p = .400) were not significant.
3.4.2.2. Recovery. For SCL during recovery following the speech, the Time × number of
anxiety labels interactions from Time 1 to Time 2 (p = .926), Time 2 to Time 3 (p = .969), and
Time 1 to Time 3 (p = .896) were not significant.
3.4.3. Non-specific skin conductance response.
3.4.3.1. Anticipation. Results are displayed in Figure 20. For SCR-NS during
anticipation of giving a speech, the Time × number of anxiety labels interaction from Time 1 to
Time 2 was not significant (p = .402). The interactions from Time 2 to Time 3 (b = -1.42, CI = -
2.8 to 0, p = .045), and Time 1 to Time 3 were significant (b = -1.92, CI = -3.2 to -.6, p = .004)
such that participants who used more affect labels during exposure had a steeper decline in SCR-
NS over time. Tests of the difference between SCR-NS during anticipation for participants at
+1SD and -1SD from the mean revealed no significant difference at Time 1 or Time 2 (ps >
.117), and a significant difference at Time 3 (difference = 1.70, p = .001) such that participants at

40
+1SD from the mean on use of anxiety labels had fewer SCR-NS during anticipation of giving a
speech than did participants at -1SD from the mean.
3.4.3.2. Recovery. For SCR-NS during recovery following the speech, the Time ×
number of anxiety labels interactions from Time 1 to Time 2 (p = .574), Time 2 to Time 3 (p =
.321), and Time 1 to Time 3 (p = .151) were not significant.
3.4.4. Personal Report of Public Speaking Anxiety. Results are displayed in Figure 21.
For PRPSA, the Time × number of anxiety labels interaction from Time 2 to Time 3 was not
significant (p = .961). The interaction from Time 1 to Time 2 (b = 15.76, CI = 1.6 to 29.9, p =
.029) was significant, and the interaction from Time 1 to Time 3 was marginally significant (b =
15.40, CI = -2.7 to 33.5, p = .095) such that participants who used fewer affect labels during
exposure had a steeper decline in PRPSA over time (interaction f2 = .05). Tests of the difference
between PRPSA for participants at +1SD and -1SD from the mean on number of anxiety labels
revealed no significant difference at Time 1 (p = .368), and significant differences at Time 2
(difference = 11.70, p = .011) and Time 3 (difference = 11.52, p = .032) such that participants at
+1SD from the mean on use of anxiety labels had higher PRPSA scores than did participants at -
1SD from the mean.
3.4.5. Subjective Units of Distress. Results are displayed in Figure 22. For SUDS, the
Time × number of anxiety labels interaction from Time 2 to Time 3 was not significant (p =
.850). The interaction from Time 1 to Time 2 was significant (b = 1.72, CI = .3 to 3.2, p = .019),
and the interaction from Time 1 to Time 3 was marginally significant (b = 1.58, -.1 to 3.2, p =
.058) such that participants who used fewer affect labels during exposure had a steeper decline in
SUDS over time (interaction f2 = .05). Tests of the difference between SUDS for participants at
+1SD and -1SD from the mean on number of anxiety labels revealed a marginally significant

41
difference at Time 1 (difference = .67, p = .083), and significant differences at Time 2
(difference = 1.52, p < .001) and Time 3 (difference = 1.45, p = .003) such that participants at
+1SD from the mean on use of anxiety labels had higher SUDS scores than did participants at -
1SD from the mean.
3.4.6. Self-Statements During Public Speaking.
3.4.6.1. Positive. For SSPS Positive, the Time × number of anxiety labels interactions
from Time 1 to Time 2 (p = .887), Time 2 to Time 3 (p = .760) and Time 1 to Time 3 (p =
.938) were not significant.
3.4.6.2. Negative. For SSPS Negative, the Time × number of anxiety labels interactions
from Time 1 to Time 2 (p = .615), Time 2 to Time 3 (p = .966), and Time 1 to Time 3 (p =
.984) were not significant.
3.4.7. Performance Rating Form. Results are displayed in Figure 23 (higher scores
indicate better self-rated performance). For PRF, the Time × number of anxiety labels
interactions from Time 2 to Time 3 (p = .144) and Time 1 to Time 3 were not significant (p
=
.501). The interaction from Time 1 to Time 2 was significant (b = -9.87, CI = -18.0 to -1.8, p =
.017) such that participants who used fewer affect labels during exposure had a steeper increase
in PRF over time (interaction f2 = .15). Tests of the difference between PRF scores for
participants at +1SD and -1SD from the mean on number of anxiety labels revealed a marginally
significant difference at Time 1 (difference = 4.86, p = .054), and significant differences at Time
2 (difference = 9.76, p < .001) and Time 3 (difference = 6.67, p = .024) such that participants at
+1SD from the mean on use of anxiety labels had lower PRF scores than did participants at -1SD
from the mean.

42
3.4.8. Optional speech. For optional speech, the Time × number of anxiety labels
interaction from Time 1 to Time 3 was not significant (p = .666).
3.5. Aim 3. Does Incidental Emotion Regulation at Baseline Moderate or Predict Response
to Exposure with Affect Labeling Versus Exposure Alone?
For each dependent variable, incidental emotion regulation is first tested as a moderator
of response to exposure plus affect labeling versus exposure alone. The significance of the Time
× Group × incidental emotion regulation interactions from Time 1 to Time 2, Time 2 to Time 3,
and Time 1 to Time 3 are reported. For significant and marginally significant interactions, the
following simple effects are tested: (1) Group mean differences at Time 1, Time 2, and Time 3 at
+1SD and -1SD from the mean of incidental emotion regulation. (2) Group slope differences
from Time 1 to Time 2, Time 2 to Time 3, and/or Time 1 to Time 3 (depending on significant
interactions) at +1SD and -1SD from the mean of incidental emotion regulation.
When the three-way interaction is either marginally significant or not significant,
incidental emotion regulation is tested as a predictor of treatment outcome, and the significance
of the Time × incidental emotion regulation interaction is reported for Time 1 to Time 2, Time 2
to Time 3, and Time 1 to Time 3. For significant and marginally significant interactions, tests of
whether participants at -1SD from the mean on incidental emotion regulation differ from those at
+1SD from the mean at Time points 1, 2 and 3.
3.5.1. Heart rate.
3.5.1.1. Anticipation. Moderation results are displayed in Figure 24. For HR during
anticipation of giving a speech, the Time × Group × incidental emotion regulation interactions
from Time 1 to Time 2 (p = .269) and Time 2 to Time 3 (p = .344) were not significant,
whereas the interaction from Time 1 to Time 3 was significant (b = 7.56, CI = .3 to 14.9, p

43
= .042)

44
(interaction f2 = .04). Tests of group mean differences at -1SD and +1SD from the mean
revealed no differences at Time 1 (ps > .745), or Time 2 (ps > .443). At Time 3, for participants
at -1SD from the mean on incidental emotion regulation, participants in the AL group had
significantly lower HR than did participants in the Control group (difference = 6.77, p = .014).
No group difference was found for participants at +1SD from the mean on incidental emotion
regulation at Time 3 (p = .592). Tests of Group slope differences from Time 1 to Time 3
revealed that for participants at -1SD from the mean on incidental emotion regulation, the AL
group had a significantly more negative slope than did the Control group (slope difference =
7.57, p = .019). No group slope difference was found for participants at +1SD from the mean on
incidental emotion regulation (p = .543).
3.5.1.2. Recovery. Moderation results are displayed in Figure 25. For HR during
recovery following the speech, the Time × Group × incidental emotion regulation interaction
from Time 1 to Time 2 was not significant (p = .446), whereas the interaction from Time 2 to
Time 3 was marginally significant (b = 5.09, CI = -.3 to 12.5, p = .063), and the interaction from
Time 1 to Time 3 was significant (b = 8.48, CI = 2.2 to 14.8, p = .008) (interaction f2 = .07).
Tests of group mean differences at -1SD and +1SD from the mean revealed no differences at
Time 1 (ps > .207) or Time 2 (ps > .301). At Time 3, for participants at -1SD from the mean on
incidental emotion regulation, participants in the AL group had marginally significantly lower
HR than participants in the Control group (difference = 4.72, p = .061). No group mean
differences were observed for participants at +1SD from the mean on incidental emotion
regulation at Time 3 (p = .329). Tests of Group slope differences from Time 1 to Time 3
revealed that for participants at -1SD from the mean on incidental emotion regulation, the AL
group had a significantly more negative slope than did the Control group (slope difference =

45
7.56, p = .007). No group slope difference was observed for participants at +1SD from
the mean on incidental emotion regulation (p = .262).
3.5.2. Skin conductance level.
3.5.2.1. Anticipation. For SCL during anticipation of giving a speech, the Time × Group
× incidental emotion regulation interactions from Time 1 to Time 2 (p = .602), Time 2 to
Time 3 (p = .218), and Time 1 to Time 3 (p = .449) were not significant.
For SCL during anticipation of giving a speech, the Time × incidental emotion regulation
interactions Time 1 to Time 2 (p = .664), Time 2 to Time 3 (p = .153), and from Time 1 to Time
3 (p = .296) were not significant.
3.5.2.2. Recovery. For SCL during recovery following the speech, the Time × Group ×
incidental emotion regulation interactions from Time 1 to Time 2 (p = .272), Time 2 to Time 3 (p
= .218) and Time 1 to Time 3 (p = .578) were not significant.
For SCL during recovery following the speech, the Time × incidental emotion regulation
interactions from Time 1 to Time 2 (p = .565), Time 2 to Time 3 (p = .153), and Time 1 to Time
3 (p = .120) were not significant.
3.5.3. Non-specific skin conductance response.
3.5.3.1. Anticipation. For SCR-NS during anticipation of giving a speech, the Time ×
Group × incidental emotion regulation interactions from Time 1 to Time 2 (p = .906), Time 2 to
Time 3 (p = .369), and Time 1 to Time 3 (p = .267) were not significant.
Predictor results are displayed in Figure 26. For SCR-NS during anticipation of giving a
speech, the Time × incidental emotion regulation interactions from Time 1 to Time 2 (p = .180)
and Time 1 to Time 3 were not significant (p = .125), whereas the Time × incidental emotion
regulation interaction from Time 2 to Time 3 was significant (b = .53, CI = .1 to .9, p = .009)

46
such that participants with deficits in incidental emotion regulation had more negative slopes
from Time 2 to Time 3 than did participants with strengths in incidental emotion regulation.
Tests of the difference between SCR-NS during anticipation for participants at +1SD and -1SD
from the mean revealed no significant differences at Time 1 or Time 3 (ps > .331), and a
significant difference at Time 2 (difference = .90, p = .032) such that participants at +1SD from
the mean on incidental emotion regulation had lower SCR-NS than did participants at -1SD
from the mean.
3.5.3.2. Recovery. Moderator results are displayed in Figure 27. For SCR-NS during
recovery following the speech, the Time × Group × incidental emotion regulation interaction
from Time 1 to Time 3 was not significant (p = .419), whereas the interaction from Time 2 to
Time 3 was marginally significant (b = -1.74, CI = -3.7 to .2, p = .080), and the interaction from
Time 1 to Time 2 was significant (b = 2.37, CI = .5 to 4.2, p = .012). Tests of group mean
differences at -1SD and +1SD revealed no differences at Time 1 (ps > .432) or Time 3 (ps >
.200). At Time 2, for participants at +1SD from the mean on incidental emotion regulation,
participants in the AL Group had significantly higher SCR-NS than participants in the Control
group (difference = .48, p = .010). At Time 2, no group differences emerged for participants at -
1SD from the mean on incidental emotion regulation (p = .487). Tests of Group slope
differences from Time 1 to Time 2 revealed that for participants at +1SD from the mean on
incidental emotion regulation, the AL group had a significantly more positive slope than did the
Control group (slope difference = .58, p = .027). No group slope difference was observed for
participants at -1SD from the mean on incidental emotion regulation (p = .236). Tests of Group
slope differences from Time 2 to Time 3 revealed that for participant at +1SD from the mean on
incidental emotion regulation, the AL group had a significantly more negative slope than did the

47
Control group (slope difference = .71, p = .027). No group slope difference was observed for
participants at -1SD from the mean on incidental emotion regulation (p = .670).
3.5.4. Personal Report of Public Speaking Anxiety. For PRPSA, the Time × Group ×
incidental emotion regulation interactions from Time 1 to Time 2 (p = .389), Time 2 to Time 3 (p
= .787), and Time 1 to Time 3 (p = .656) were not significant.
For PRPSA, the Time × incidental emotion regulation interactions from Time 1 to Time
2 (p = .470), Time 2 to Time 3 (p = .270) and Time 1 to Time 3 (p = .165) were not significant.
3.5.5. Subjective Units of Distress. Moderator results are displayed in Figure 28. For
SUDS, the Time × Group × incidental emotion regulation interactions from Time 1 to Time 3 (p
= .838) and Time 2 to Time 3 (p = .138) were not significant, whereas the interaction from Time
1 to Time 2 was marginally significant (b = -.81, CI = -1.7 to .1, p = .085) (interaction f2 = .05).
Tests of group mean differences at -1SD and +1SD from the mean on incidental emotion
regulation revealed no differences at Time 1 (ps > .457), Time 2 (ps > .102) or Time 3 (ps >
.786). Tests of Group slope differences from Time 1 to Time 2 revealed no differences at +1SD
or -1SD from the mean on incidental emotion regulation (ps > .122).
Predictor results are displayed in Figure 29. For SUDS, the Time × incidental emotion
regulation interactions from Time 1 to Time 2 (p = .376) and Time 2 to Time 3 (p = .248) were
not significant. The interaction from Time 1 to Time 3 was marginally significant (b = .46, CI =
0 to .9, p = .061) such that greater deficits in incidental emotion regulation were associated with
greater decreases in SUDS over Time (interaction f2 = .01). Tests of the difference between
SUDS for participants at +1SD and -1SD from the mean on incidental emotion regulation
revealed no significant differences at Time 1, Time 2, or Time 3 (ps > .113).
3.5.6. Self Statements During Public Speaking.

48
3.5.6.1. Positive. Moderator results for SSPS Positive are displayed in Figure 30 (higher
scores indicate more positive cognitions). For SPSS Positive, the Time × Group × incidental
emotion regulation interactions from Time 2 to Time 3 (p = .634) and Time 1 to Time 3 (p =
.272) were not significant, whereas the interaction from Time 1 to Time 2 was marginally
significant (b = 2.15, CI = -.1 to 4.3, p = .055) (interaction f2 = .06). Tests of group mean
differences at -1SD and +1SD from the mean on incidental emotion regulation revealed no
differences at Time 1 (ps > .440). At Time 2, for participants at -1SD from the mean on
incidental emotion regulation, participants in the AL Group had marginally significantly lower
SSPS Positive scores than participants in the Control group (difference = 1.77, p = .096). No
group differences emerged for participants at +1SD from the mean on incidental emotion
regulation at Time 2 (p = .585). At Time 3, for participants at -1SD from the mean on incidental
emotion regulation, participants in the AL Group had marginally significantly lower SSPS
Positive scores than participants in the Control group (difference = 2.20, p = .071). No group
differences emerged for participants at +1SD from the mean on incidental emotion regulation at
Time 3 (p = .653). Tests of Group slope differences from Time 1 to Time 2 revealed no
differences at +1SD or -1SD from the mean on incidental emotion regulation (ps > .141).
Predictor results for SSPS Positive are displayed in Figure 31 (higher scores indicate
more positive cognitions). For SSPS Positive, the Time × incidental emotion regulation
interaction from Time 2 to Time 3 was not significant (p = .605). The interactions from Time 1
to Time 2 (b = -1.28, CI = -2.3 to -.2, p = .016) and Time 1 to Time 3 (b = -1.56, CI = -2.9 to -.2,
p = .025) were significant such that greater deficits in incidental emotion regulation were
associated with greater increase in SSPS Positive over Time (f2 = .01). Tests of the difference in
SSPS Positive for participants at +1SD and -1SD from the mean on incidental emotion

49
regulation revealed no significant differences at Time 2, or Time 3 (ps > .746). At Time 1,
participants at +1SD from the mean on incidental emotion regulation had significantly higher
SSPS Positive scores than did participants at -1SD from the mean (difference = 1.70, p = .025).
3.5.6.2. Negative. Moderator results for SSPS Negative are displayed in Figure 32. For
SPSS Negative, the Time × Group × incidental emotion regulation interactions from Time 1 to
Time 2 (p = .389) and from Time 1 to Time 3 (p = .237) were not significant, whereas the
interaction from Time 2 to Time 3 was marginally significant (b = 2.20, CI = -.2 to 4.6, p = .068)
(interaction f2 = .03). Tests of group mean differences at -1SD and +1SD revealed no differences
at Time 1 (ps > .388), Time 2 (ps > .278), or Time 3 (p > .438). Tests of Group slope differences
from Time 2 to Time 3 revealed a marginally significant difference for participants at +1SD from
the mean on incidental emotion regulation such that the AL group had a significantly more
positive slope than did the Control group (slope difference = 1.96, p = .060). No group slope
difference was found for participants at -1SD from the mean on incidental emotion regulation
from Time 2 to Time 3 (p = .446).
Predictor results for SSPS Negative are displayed in Figure 33. For SSPS Negative, the
Time × incidental emotion regulation interaction from Time 1 to Time 2 was not significant (p =
.241). The interactions from Time 2 to Time 3 (b = 1.13, CI = 0 to 2.2, p = .047) and Time 1 to
Time 3 (b = 1.80, CI = .4 to 3.2, p = .013) were significant such that greater deficits in incidental
emotion regulation were associated with greater decreases in SSPS Negative over Time
(interaction f2 = .00). Tests of the difference in SSPS Negative for participants at +1SD and -
1SD from the mean on incidental emotion regulation revealed no significant differences at Time
2, or Time 3 (ps > .255).
At Time 1, participants at +1SD from the mean on incidental emotion

50
regulation had significantly lower SSPS Negative scores than did participants at -1SD from the
mean (difference = 1.83, p = .041).
3.5.7. Performance Rating Form. For PRF, the Time × Group × incidental emotion
regulation interactions from Time 1 to Time 2 (p = .274), Time 2 to Time 3 (p = .316), and
Time 1 to Time 3 (p = .944) were not significant.
For PRF, the Time × incidental emotion regulation interactions from Time 1 to Time 2 (p
= .470), Time 2 to Time 3 (p = .216), and from Time 1 to Time 3 (p = .165) were not significant.
3.5.8. Optional speech. For the optional speech, the Time × Group × incidental emotion
regulation interaction from Time 1 to Time 3 was not significant (p = .988).
For the optional speech, the Time × incidental emotion regulation interaction from Time
1 to Time 3 was not significant (p = .689).

51
CHAPTER 4
Discussion
The current study had three primary aims. The first aim was to test whether exposure
combined with affect labeling resulted in greater attenuation of fear responding than did
exposure alone. The second aim was to assess whether the number of anxiety labels used during
exposure in the affect labeling group predicted greater fear attenuation. The final aim was to test
whether incidental emotion regulation capacity at baseline could be used to predict who would
benefit from exposure plus affect labeling compared to exposure alone. If no moderation was
found, incidental emotion regulation was assessed as a predictor of who would respond to
exposure regardless of group assignment. All three aims were tested on the same set of
dependent variables. These included heart rate, skin conductance level, and non-specific skin
conductance response during anticipation of and recovery from a speech, self-reported trait
public speaking anxiety, anxiety level during public speaking, negative and positive self
statements during public speaking, self rated public speaking performance, and avoidance of
giving an additional speech.
4.1. Aim 1: Does Affect Labeling Enhance Exposure Effectiveness Compared to Exposure
Alone?
Consistent with hypotheses, participants in the exposure plus affect-labeling group had a
steeper decline in heart rate and non-specific skin conductance responses during recovery
following the speech than did participants in the exposure alone condition. This finding is
consistent with previous research showing that exposure combined with affect labeling results in
greater reduction in galvanic skin response than exposure alone (Kircanski et al., 2012; Tabibnia

52
et al., 2008). It is notable that the effect was found only for skin conductance response and heart
rate during recovery following the speech and not anticipation of the speech. Although research
on public speaking tasks generally focuses on anticipation of rather than recovery from speaking,
post-event processing is common in patients with social anxiety and relates both to the severity
of social anxiety symptoms and predicts subsequent avoidance of similar social situations
(Rachman, Grüter-Andrew, & Shafran, 2000). Therefore, the effect of affect labeling on
reducing physiological activation during recovery following the speech may reflect reduction in
negative post event processing and rumination.
Additional analyses were conducted comparing participants in the exposure alone
condition to those in the exposure plus affect labeling condition who were “high” labelers (i.e. in
the top 50th percentile of number of labels chosen). Because there were participants who chose
no or very few affect labels during exposure, limiting the sample to those in the top 50th
percentile included only those participants who chose at least 7 labels (out of 20 possible) during
exposures. When only high labelers were included in the group comparison, consistent with
hypotheses, participants in the affect labeling group had marginally significantly lower heart rate
and significantly fewer non-specific skin conductance responses during anticipation of giving a
speech, and significantly lower heart rate and marginally significantly fewer non-specific skin
conductance responses during recovery following the speech. Although these findings replicate
previous research, causality cannot be inferred given that participants were not randomly
assigned to the high labeling group within the affect labeling condition. It is possible that high
labelers in the affect labeling condition differed in some meaningful way from participants
assigned to the exposure alone condition that explains the significant group differences.
However, it is important to note that the analytic approach controlled for baseline levels of the

53
dependent variables, so group differences at time points 2 and 3 cannot be explained by
preexisting baseline group differences on the dependent measures. Because many participants
did not choose the affect labels provided, a more effective approach for future studies may be to
allow participants to generate their own affective labels as in Kircanski et al (2012). However,
researchers have yet to assess whether matching participants’ labels to their own affective
experience produces greater benefit than providing predetermined labels from which participants
can choose. Regardless of whether participants generate their own labels or not, future studies
should ensure that all participants in the labeling group engage, at least to some extent, in affect
labeling and are not given the option to completely refrain from labeling.
Contrary to hypotheses, on self-report measures of anxiety, participants in the affect
labeling condition had marginally significantly less improvement in self rated performance
than participants in the exposure alone condition. In addition, high labelers in the affect
labeling condition had marginally significantly less improvement in trait public speaking
anxiety and anxiety while speaking than did participants in the exposure alone condition.
These findings however were limited to the change from Time 1 to Time 2 and were no longer
significant at Time 3, and no group differences remained by the third time point. In a previous
study, the benefit of affect labeling during exposure was found only for galvanic skin response
and not for self-report measures (Kircanski et al., 2012). One possible explanation provided by
Kircanski and colleagues is that people tend to predict that affect labeling will not be an
effective strategy for reducing distress (Lieberman et al., 2011). Another possibility is that by
repeatedly labeling anxiety and feared outcomes during exposure, high labelers in the affect
labeling group were trained to report increased anxiety symptoms on self report measures
administered during subsequent assessments. Consistent with mindfulness based approaches to

54
the treatment of

55
anxiety such as Acceptance and Commitment Therapy (ACT), it is possible that participants
who engaged in affect labeling became more willing to report anxiety symptoms at follow-up
assessments, but were less distressed by these symptoms, and therefore less physiologically
reactive. A phrase often used in ACT regarding mindfulness practice is that the goal is not to
feel better, but to get better at feeling (Hayes et al., 1999). Therefore, although not assessed in
the current study, perhaps through labeling, participants became more attuned to and accepting
of their emotions and anxiety symptoms, which led to increased symptom reporting, but
decreased physiological activation. Future studies that include training in affect labeling should
measure acceptance of anxiety in addition to anxiety symptoms.
Inconsistent with previous research (Kircanski et al., 2012), we did not find that affect
labeling reduced avoidance of public speaking. This failure to replicate previous findings may
be attributable to floor effects on our measure of avoidance that limited statistical power to
detect group differences. Participants were given the option to give an additional speech in
exchange for $5. Although approximately 39% of participants avoided the additional speech at
the baseline assessment, following exposure and at one-week follow-up, only 13% of
participants avoided the additional speech. Given the sample size, this dichotomous outcome did
not allow enough variability to detect group differences. Future studies should use a measure of
avoidance that allows for greater variability (e.g. amount of time speaking) or should use a larger
sample size to increase statistical power.
4.2. Aim 2: Does the Number of Anxiety Related Words Used During Exposure Predict
Greater Attenuation of Fear Responding at Re-Test?
Consistent with hypotheses, the more anxiety labels participants chose during exposure,
the fewer non-specific skin conductance responses participants had during anticipation of giving

56
a speech by the one-week follow-up. These findings are consistent with previous research in
spider fearful participants where it was found that participants who used more anxiety words
during affect labeling had a greater reduction in spontaneous skin conductance response at re-test
than did participants who used fewer anxiety words (Kircanski et al., 2012). Perhaps the use of
more affect labels during exposure lead to greater activation in PFC-Amygdala pathways. If
participants with anxiety show weaker connectivity between areas of the PFC (such as
RVLPFC) and the amygdala, it is possible that the number of repetitions of activation in these
pathways during exposure is positively correlated with the strength of PFC-amygdala
connectivity following completion of exposure. Consistent with the principle of neural
plasticity, which states that repetition of a process can increase efficiency and efficacy of that
process through changes in neuron function, chemical profile, and structure (Anderson, 2010;
Kandel & Schwartz, 1982), greater activation of PFC-amygdala neural pathways as a result of
more frequent labeling may have produced greater neural change and ultimately more effective
down regulation of physiological fear responding.
Contrary to hypotheses, following exposure, participants who used fewer affect labels
during exposure showed greater improvement in trait public speaking anxiety, anxiety while
speaking, and self reported public speaking performance than did participants who used more
affect labels during exposure. Consistent with findings from study Aim 1, self reported
symptoms did not align with physiological measures of anxious responding. Perhaps
participants who chose more anxiety labels during exposure reported more symptoms in order to
maintain consistency across different self-report assessments. Festinger’s theory of cognitive
dissonance (1957) suggests that individuals are motivated to maintain internal consistency, and
discomfort arises when beliefs and actions are inconsistent across different settings. Therefore,

57
perhaps when participants engaged in more frequent labeling of negative emotions, in order for
their responses to be consistent from one setting to the next, they reported more anxiety
symptoms despite having less physiological arousal. Given a longer lag time between labeling
and the assessment of self-report symptoms, perhaps the importance of consistency on self-report
measures would be diminished. It is also possible that, had participants been followed for a
longer period of time, those who labeled more frequently would show continued improvement on
self-report measures, while those who labeled less frequently would show a return of symptoms.
4.3. Aim 3: Does Incidental Emotion Regulation at Baseline Moderate or Predict Response
to Exposure with Affect Labeling Versus Exposure Alone?
Contrary to hypotheses, we found that participants who had deficits incidental emotion
regulation at baseline benefited more from exposure combined with affect labeling than exposure
alone on measures of physiology including heart rate during speech anticipation and recovery,
and non-specific skin conductance responses during recovery. Based on previous research that
supports the matching hypothesis (Engebretson, Matthews, & Scheier, 1989; Niles et al., 2014;
Stanton et al., 2000), we hypothesized that participants with strengths in incidental emotion
regulation at baseline would show greater benefit from an intervention that included affect
labeling. Previous research however did not measure physiological activation as the outcome,
but instead measured self-reported symptoms. Therefore, the differences in findings may be
attributed to the different method of outcome assessment. In healthy participants, affect labeling
leads to a reduction in self-reported distress while viewing negative images by increasing
activation in areas of the PFC and decreasing activation in the amygdala. It is possible that
participants who showed less benefit from incidental emotion regulation have greater deficits in
PFC-Amygdala connectivity, and as a result benefited more from an intervention that

58
specifically targeted these connectivity deficits. Neural activation however was not directly
assessed in the current project, and future studies that include affect labeling as a strategy for
enhancing exposure effectiveness would benefit from inclusion of measures of neural activation
before and after the intervention.
Contrary to hypotheses, from Time 1 to Time 2, we found that participants with greater
deficits in incidental emotion regulation did better in exposure alone than exposure plus affect
labeling on self-reported negative and positive cognitions and anxiety during public speaking.
Results should be interpreted with caution given that effects were marginally significant and
were not maintained at one-week follow-up. Consistent with findings from study Aims 1 and 2,
findings on the self-report measures were not consistent with findings on the physiological
measures. Again, one possibility is that by labeling anxiety and feared outcomes during
exposure, participants in the affect labeling group were trained to report increased anxiety
symptoms on self report measures administered during subsequent BATs. The moderation
effects however suggest that only participants with deficits in incidental emotion regulation later
reported more symptoms. It is possible that these participants’ incidental emotion regulation
ability improved, and as a result, they were more likely to report symptoms because they found
this strategy more effective at reducing physiological arousal.
For marginally significant moderator findings, incidental emotion regulation capacity
was also tested as an overall predictor of outcome (regardless of group). Significant prediction
effects were found for negative and positive cognitions during public speaking, and a marginally
significant effect was found for self-reported anxiety during public speaking. Across all three
dependent measures, participants with deficits in incidental emotion regulation at baseline
showed the greatest improvement in anxious responding following exposure. More specifically,

59
participants with greater deficits in incidental emotion regulation reported significantly more
anxiety symptoms at baseline than participants with less deficit, but following completion of
exposure, those with deficits no longer differed from those without deficits. Because incidental
emotion regulation is a proxy for prefrontal-amygdala connectivity, these findings imply that
exposure, regardless of the inclusion of affect labeling, is particularly effective for participants
with greater deficits in prefrontal-amygdala circuitry.
4.4. Differential Findings for Self-Report and Physiological Measurement
The lack of synchrony between the physiological measurement and self reported anxiety
is an important consideration for research on the treatment of anxiety. At baseline, the increase
in heart rate, skin conductance level, and non-specific skin conductance responses during
anticipation did not correlate with self-report measures of anxiety. The only significant
correlation with a self-report measure was found between non-specific skin conductance
fluctuation increase during anticipation and depressive symptoms. This suggests that physiology
may index a different facet of anxious responding than does self-reported anxiety. It is also
notable that the only significant correlate of increased avoidance of the optional speech at
baseline was the amount of increase in skin conductance response from baseline to recovery.
Self-report measures of anxiety were not significantly associated with behavioral avoidance.
Given the importance of avoidance in the maintenance of anxiety disorders, physiology,
particularly during recovery following a stressor, may be an important indicator of disorder
severity in addition to self-reported symptoms.
4.5. Summary and Implications
In sum, the current research supports the theory that affect labeling can enhance exposure
effectiveness. Patients with anxiety show deficits in prefrontal amygdala connectivity (Hahn et

60
al., 2011; Kim et al., 2011), and repeated activation of prefrontal regions that project to the
amygdala through exposure and affect labeling can lead to a reduction in physiological activation
in response to an anxiety provoking stimulus. The results of the current study indicate that the
more a fearful individual labels their emotional experience during exposure, the greater the
reduction in galvanic skin response and heart rate (measures of fear arousal) when they next
encounter the feared stimulus. The benefit of affect labeling was not shown for self-reported
anxiety, which may require longer-term follow up than was possible in the current study.
Finally, adding affect labeling to exposure was particularly beneficial (on physiological
outcomes only) for individuals who showed deficits in incidental emotion regulation, which is an
indicator of poor prefrontal-amygdala connectivity. This finding provides further evidence that
targeting prefrontal-amygdala circuitry in anxiety patients using tasks that activate key regions
involved in emotion regulation can improve treatment effectiveness, and that such interventions
will be particularly effective for patients who show the greatest deficits in this circuit.

61
Table 1. Measures Used at Each Stage of the Study.
BAT-1 Exp-1 Exp-2 BAT-2 BAT-3
MINI X
PRPSA X X X
SSPS X X X
PHQ X X X
SPIN X X X
PRF X X X
SUDS X X X X X
HR, SCR-NS, SCL X X X
Optional Speech X X X
% Anxiety Labels X X
Incidental Emotion Regulation X
ECQ X
Note. MINI=MINI Neuropsychiatric Interview for Social Anxiety; PRPSA=Personal Report of
Public Speaking Anxiety; SSPS=Self-Statements During Public Speaking Questionnaire;
PHQ=Patient Health Questionnaire; SPIN=Social Phobia Inventory; PRF=Performance Rating
Form; SUDS=Subjective Units of Distress Scale; HR=Heart Rate; SCR-NS=Non Specific Skin
Conductance Response; SCL=Skin Conductance Level; % Anxiety Labels=Percent of anxiety
labels chosen; ECQ=Exposure Credibility Questionnaire

62
Table 2. Number of Missing Data Points and Reason for Missing Data for Study Variables by
Time Point
Time 1 Time 2 Time 3 Reasons Missing
Age 6 -- -- Participant Did Not Complete
Experimenter Error
Gender 0 -- --
Ethnicity 5 -- -- Participant Did Not Complete
Experimenter Error
Write in a Journal 10 -- -- Participant Did Not Complete
Experimenter Error
Student 3 -- -- Participant Did Not Complete
Experimenter Error
English First Language 5 -- -- Participant Did Not Complete
Experimenter Error
Born in United States 7 -- -- Participant Did Not Complete
Experimenter Error
MINI 1 -- -- Inadvertently Deleted
PRPSA 4 2 1 Inadvertently Deleted
SSPS 5 2 1 Inadvertently Deleted
Experimenter Error
PHQ 4 2 1 Inadvertently Deleted
SPIN 4 2 1 Inadvertently Deleted
PRF 5 2 1 Inadvertently Deleted
Experimenter Error
SUDS 1 0 0 Computer Program Failure
HR 1 2 1 Experimenter Error
SCR-NS/SCL 9 10 7 Participant Non Response
Optional Speech 0 0 0
% Anxiety Labels 0 0 --
Incidental Emotion 8 -- -- Participant Did Not Complete
Regulation Experimenter Error
ECQ 2 -- -- Experimenter Error
Note. MINI=MINI Neuropsychiatric Interview for Social Anxiety; PRPSA=Personal Report of
Public Speaking Anxiety; SSPS=Self-Statements During Public Speaking Questionnaire;
PHQ=Patient Health Questionnaire; SPIN=Social Phobia Inventory; PRF=Performance Rating
Form; SUDS=Subjective Units of Distress Scale; HR=Heart Rate; SCR-NS=Non Specific Skin
Conductance Response; SCL=Skin Conductance Level; % Anxiety Labels=Percent of anxiety
labels chosen; ECQ=Exposure Credibility Questionnaire

63
Table 3. Descriptive Statistics and Tests of Baseline Group Differences for Demographics
Overall (n=100) AL (n=52) Control (n=48) Statistical Test
Age (mean (sd)) 25.3 (9.1) 24.7 (8.9) 26.1 (9.3) t(92) = .7
Female
Ethnicity
80% (80/100) 77% (40/52) 83% (40/48) χ2(1) = .6
Fisher’s p = .83a
Asian 55% (52/95) 57% (28/49) 52% (24/46)
Hispanic 16% (15/95) 14% (7/49) 17% (8/46)
African American 6% (6/95) 6% (3/49) 7% (3/46)
Caucasian 14% (13/95) 10% (5/49) 17% (8/46)
Other 9% (9/95) 12% (6/49) 7% (3/46)
Write in a Journal 17% (15/90) 14% (6/44) 20% (9/46) χ2(1) = .6
Student 92% (89/97) 94% (47/50) 89% (42/47) χ2(1) = .7
English First Language 63% (60/95) 63% (30/48) 64% (30/47) χ2(1) = 0
Born in United States 75% (70/93) 79% (37/47) 72% (33/46) χ2(1) = .6
Social Anxiety Disorder 36% (36/99) 35% (18/51) 38% (18/48) χ2(1) = .8
PRPSA Score 133.0 (14.7) 133.2 (14.7) 132.8 (16.1) t(94) = -.1
PHQ Score 5.6 (4.3) 5.9 (4.4) 5.3 (4.2) t(94) = -.7
SPIN Score 6.4 (3.0) 6.7 (2.8) 6.1 (3.2) t(94) = -1.0
* p < .05
aFisher’s exact test was used to test for significance due to small cell sizes
Note. AL = Affect Labeling Group; Control = Control Group; PRPSA=Personal Report of Public
Speaking Anxiety; PHQ=Patient Health Questionnaire; SPIN=Social Phobia Inventory

64
Table 4. Descriptive Statistics by Group and Time for BAT Measures
AL Control
Speech (%)
Note. HR=Heart Rate; SCL=Skin Conductance Level; SCR-NS=Non Specific Skin Conductance
Response; PRPSA=Personal Report of Public Speaking Anxiety; SUDS=Subjective Units of
Distress Scale; SSPS=Self-Statements During Public Speaking Questionnaire;
PRF=Performance Rating Form
T1 (n=52) T2 (n=43) T3 (n=41) T1 (n=48) T2 (n=42) T3 (n=40)
Mean (SD)
HR
Baseline 77.1 (12.6) 77.3 (11.7) 77.4 (12.5) 72.4 (10.0) 73.9 (11.0) 76.5 (13.6)
Anticipation 81.9 (13.3) 81.3 (12.2) 80.4 (13.3) 78.3 (12.1) 78.1 (11.9) 79.8 (13.1)
Recovery 75.5 (13.1) 75.5 (10.5) 74.7 (12.7) 71.4 (9.7) 71.0 (10.3) 72.8 (12.0)
SCL
Baseline 2.0 (1.1) 1.9 (1.2) 1.9 (1.2) 2.1 (1.1) 1.8 (1.1) 2.1 (1.7)
Anticipation 3.0 (1.6) 2.6 (1.6) 2.6 (1.5) 3.0 (1.2) 2.6 (1.2) 2.9 (1.8)
Recovery 3.1 (1.4) 3.2 (1.4) 3.3 (1.2) 3.2 (1.2) 3.0 (1.2) 3.3 (1.8)
SCR-NS
Baseline .8 (1.3) .5 (1.2) .8 (1.3) .3 (.8) .2 (.8) .8 (1.4)
Anticipation 2.5 (1.9) 1.9 (2.0) 1.8 (2.4) 2.5 (1.7) 1.9 (2.2) 2.0 (1.8)
Recovery .8 (1.3) .6 (1.3) .3 (.7) .6 (.9) .4 (.7) .6 (.9)
PRPSA 133.2 (14.7) 126.2 (17.6) 122.7 (17.8) 132.8 (16.1) 121.5 (16.1) 117.3 (15.1)
SUDS 4.9 (1.4) 3.7 (1.8) 3.3 (1.8) 4.7 (1.6) 3.5 (1.5) 3.4 (1.6)
SSPS Positive 14.4 (3.9) 15.7 (3.5) 15.9 (4.1) 14.8 (4.0) 16.5 (3.3) 17.5 (3.1)
SSPS
Negative 16.5 (4.3) 14.3 (4.7) 13.4 (4.5) 16.5 (4.1) 14.2 (3.8) 12.5 (3.8)
PRF 25.7 (9.1) 35.6 (10.1) 36.9 (10.1) 24.0 (8.0) 32.6 (8.3) 37.6 (9.9)
Optional 60% (31/52) 88% (38/43) 88% (36/41) 63% (30/48) 83% (35/42) 85% (34/40)

65
Table 5. Descriptive Statistics by Group and Time for EXP measures
EXP 1 (n=49) EXP 2 (n=43)
Mean Percentage (SD)
Affect Labels
Anxiety Words 36% (26) 37% (26)
Anger Words 7% (11) 9% (11)
Sadness Words 10% (13) 10% (13)
Other 46% (35) 43% (33)
Feared Outcome 73% (34) 75% (32)
AL (n=49) Control (n=46) AL (n=43) Control (n=43)
Mean (SD)
SUDS
Beginning 4.7 (1.8) 4.0 (1.7) 3.6 (1.9) 4.0 (1.7)
End 5.1 (1.9) 4.4 (2.0) 3.8 (1.8) 3.5 (1.7)
ECQ 19.0 (5.5) 19.6 (6.4) -- --
Note. SUDS = Subjective Units of Distress; ECQ = Exposure Credibility Questionnaire
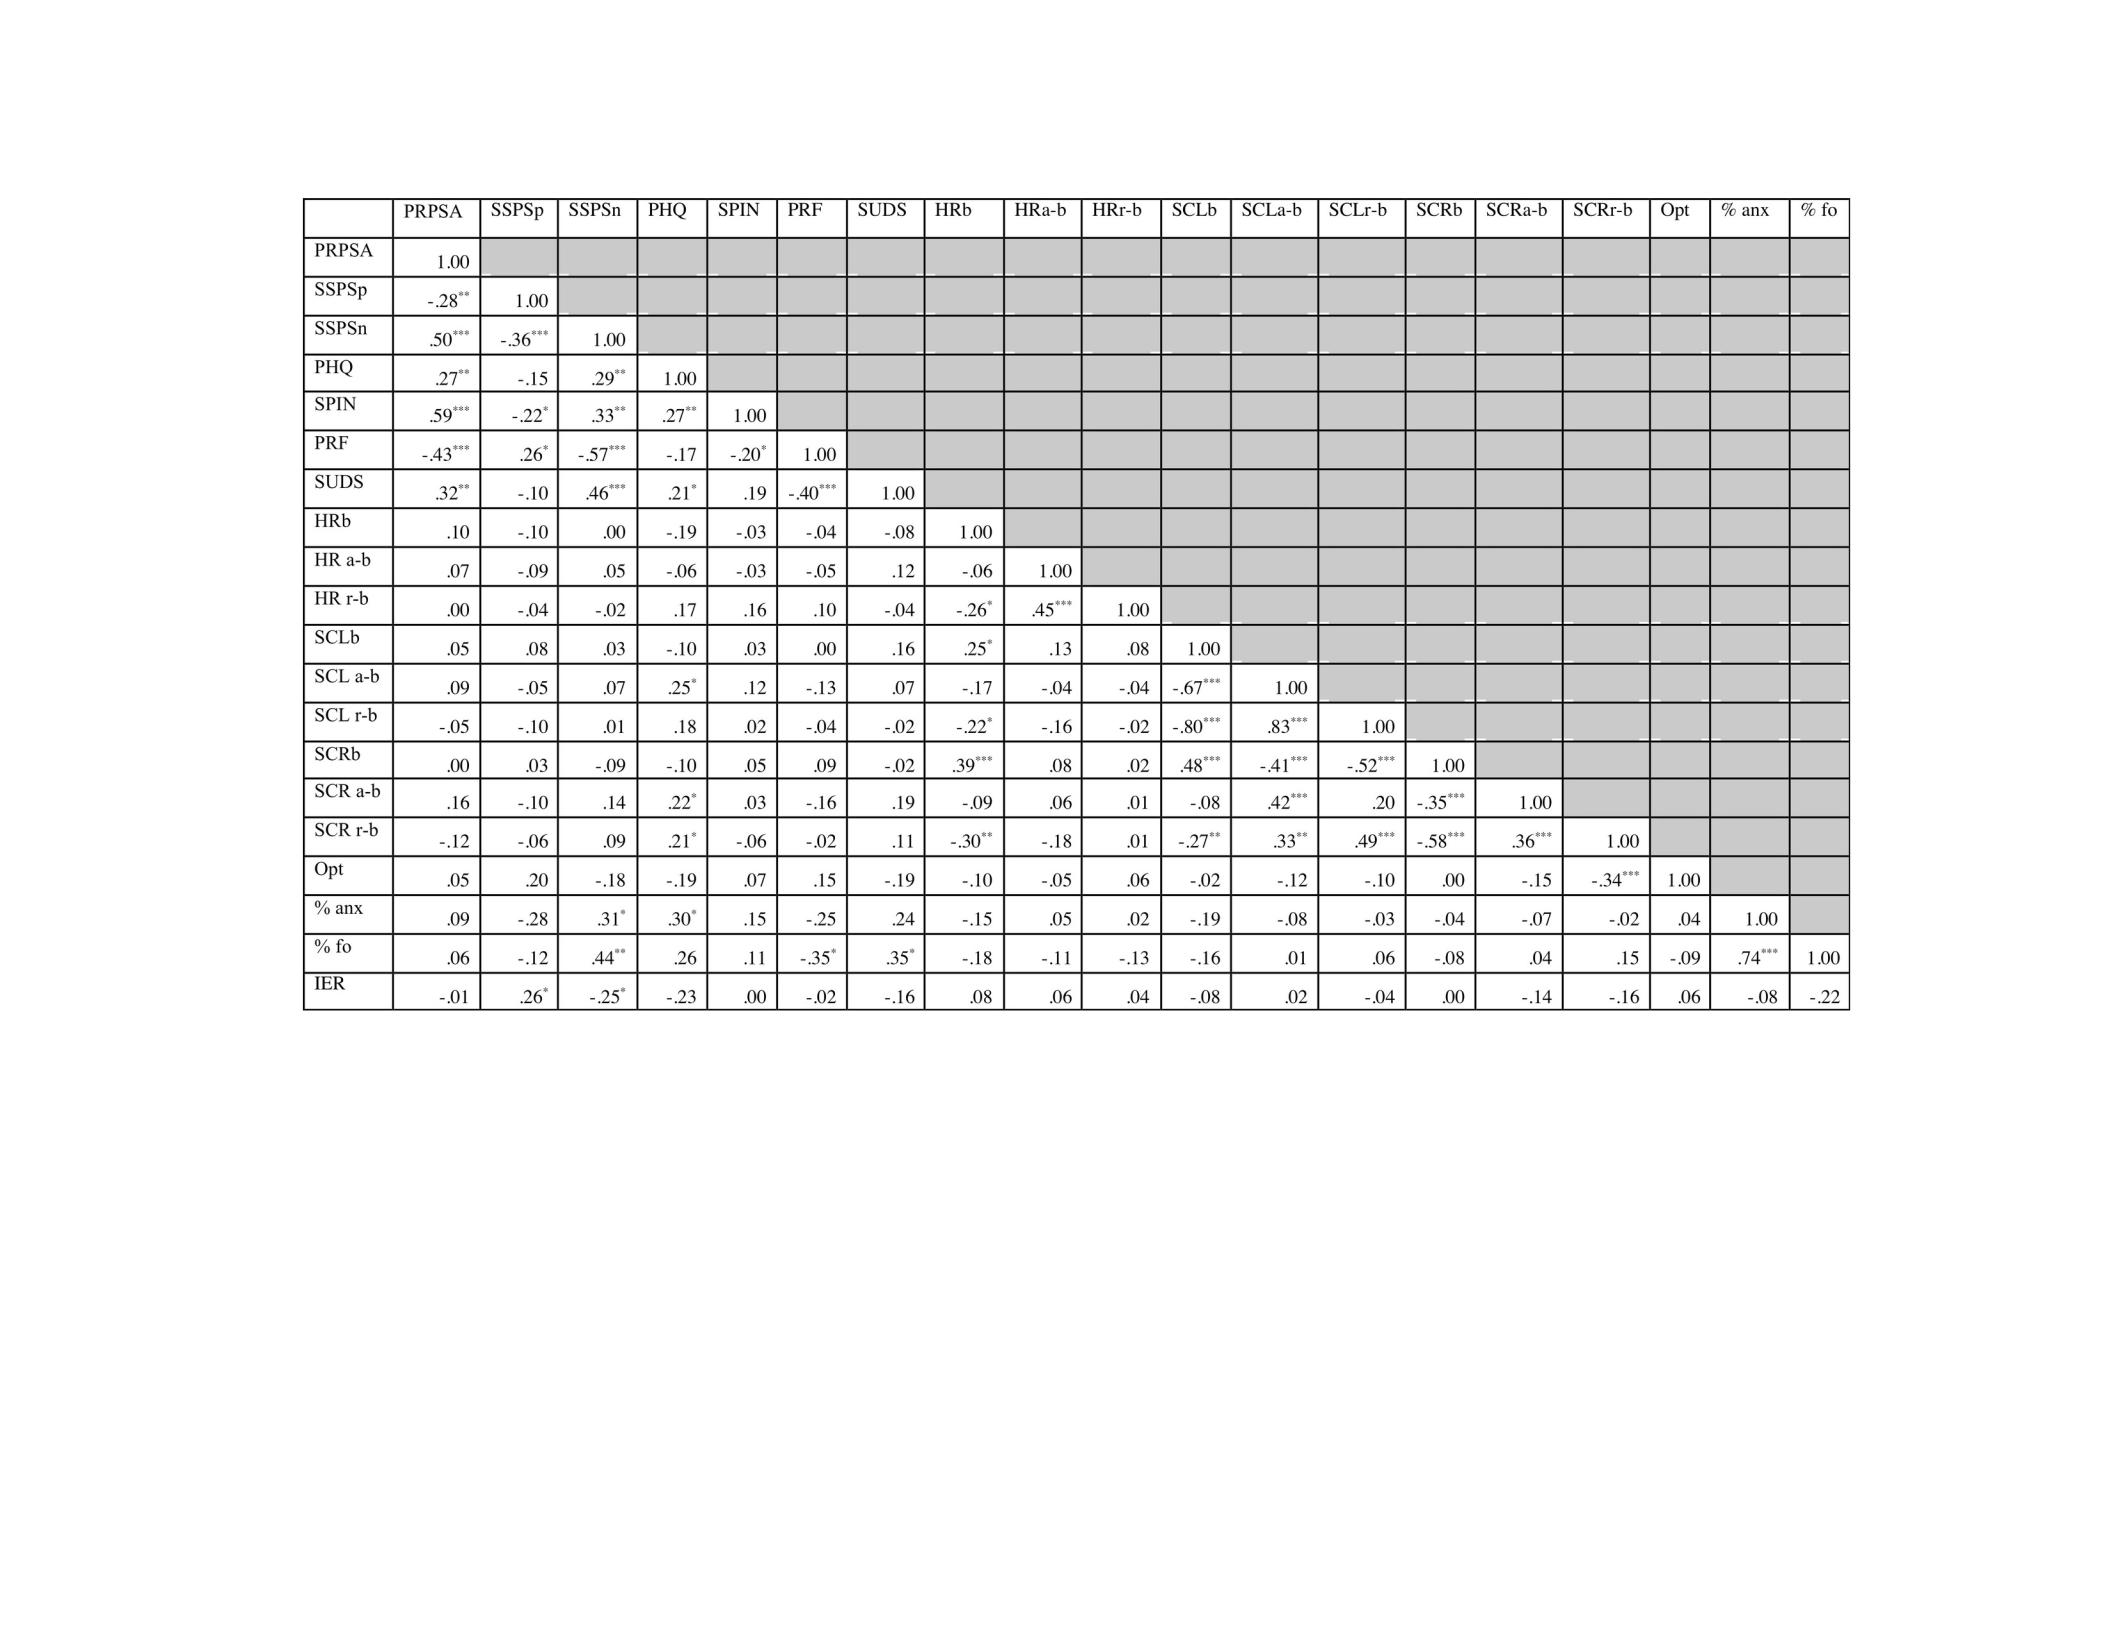
* p < .05, ** p < .01, *** p < .001
Note. PRPSA = Personal Report of Public Speaking Anxiety; SSPSp = Self Statements During Public Speaking – Positive;
SSPSn = Self Statements During Public Speaking – Negative; PHQ = Patient Health Questionnaire; SPIN = Social Phobia
Inventory; PRF = Performance Rating Form; SUDS = Subjective Units of Distress; HR = Heart Rate; SCL = Skin
Conductance Level SCR-NS = Non Specific Skin Conductance Response; b = anticipation; a-b = anticipation minus
baseline; r-b = recovery minus baseline; Opt = optional speech; % anx = percent anxiety labels chosen; % fo = percent
feared outcomes chosen; IER = Incidental Emotion Regulation
Table 6. Correlations Among Key Study Variables

62
Table 7. Descriptive Statistics Completers vs. Dropout for Relevant Study Variables
Completers (n=81) Dropout (n=19) t statistic
Mean (SD)
HR
Baseline 74.0 (11.5) 78.7 (11.6) t(97) = -1.6
Anticipation 78.9 (1.4) 85.7 (11.2) t(97) = -2.1*
Recovery
SCLa
72.5 (11.5) 78.1 (12.0) t(96) = -1.9t
Baseline .5 (.5) .5 (.7) t(89) = 0
Anticipation 1.0 (.4) 1.1 (.5) t(89) = -.9
Recovery
SCR-NSb
1.1 (.3) 1.2 (.5) t(89) = -1.0
Baseline .5 (1.2) .6 (1.2) z=.1
Anticipation 2.3 (1.7) 3.4 (1.9) z=-1.8t
Recovery .9 (1.2) .6 (1.1) z=-1.4
PRPSA 131.9 (15.1) 137.7 (16.0) t(94) = -1.4
SUDS (BAT) 4.7 (1.5) 5.0 (1.5) t(97) = -.8
SSPS Pos 15.0 (3.9) 12.8 (3.7) t(93) = 2.1*
SSPS Neg 16.4 (4.1) 16.9 (4.7) t(93) = -.5
PRF 25.7 (8.6) 20.9 (7.6) t(93) = 2.2*
Optional Speech (%) 65% (53/81) 42% (8/19) χ2(1) = 3.5t
PHQ 14.4 (4.0) 15.4 (5.4) t(94) = -.8
SPIN 9.2 (3.1) 10.1 (2.6) t(94) = -1.1
SUDS (exposure)
Beginning 4.2 (1.7) 4.9 (1.9) t(93) = -1.5
End 4.7 (2.0) 5.1 (2.0) t(88) = -.7
ECQ 19.1 (5.6) 19.8 (7.2) t(96) = -.5
t p < .10, * p < .05
a SCL values were log transformed
b Mann-Whitney test was used because variable is non-normal (count)
Note. HR=Heart Rate; SCL=Skin Conductance Level; SCR-NS=Non Specific Skin Conductance
Response; PRPSA=Personal Report of Public Speaking Anxiety; SUDS=Subjective Units of
Distress Scale; SSPS=Self-Statements During Public Speaking Questionnaire; PRF=Performance
Rating Form; PHQ = Patient Health Questionnaire; SPIN = Social Phobia Inventory; ECQ =
Exposure Credibility Questionnaire
63
Figure 1. Study Procedure
Affect
Labeling
Task
BAT-1
Exp-1 BAT-2
Exp-2
BAT-3
Enrollment
via phone
screening
Time 1 Time 2 Time 3
3 days 5 days
30 Min60 Min
75 Min
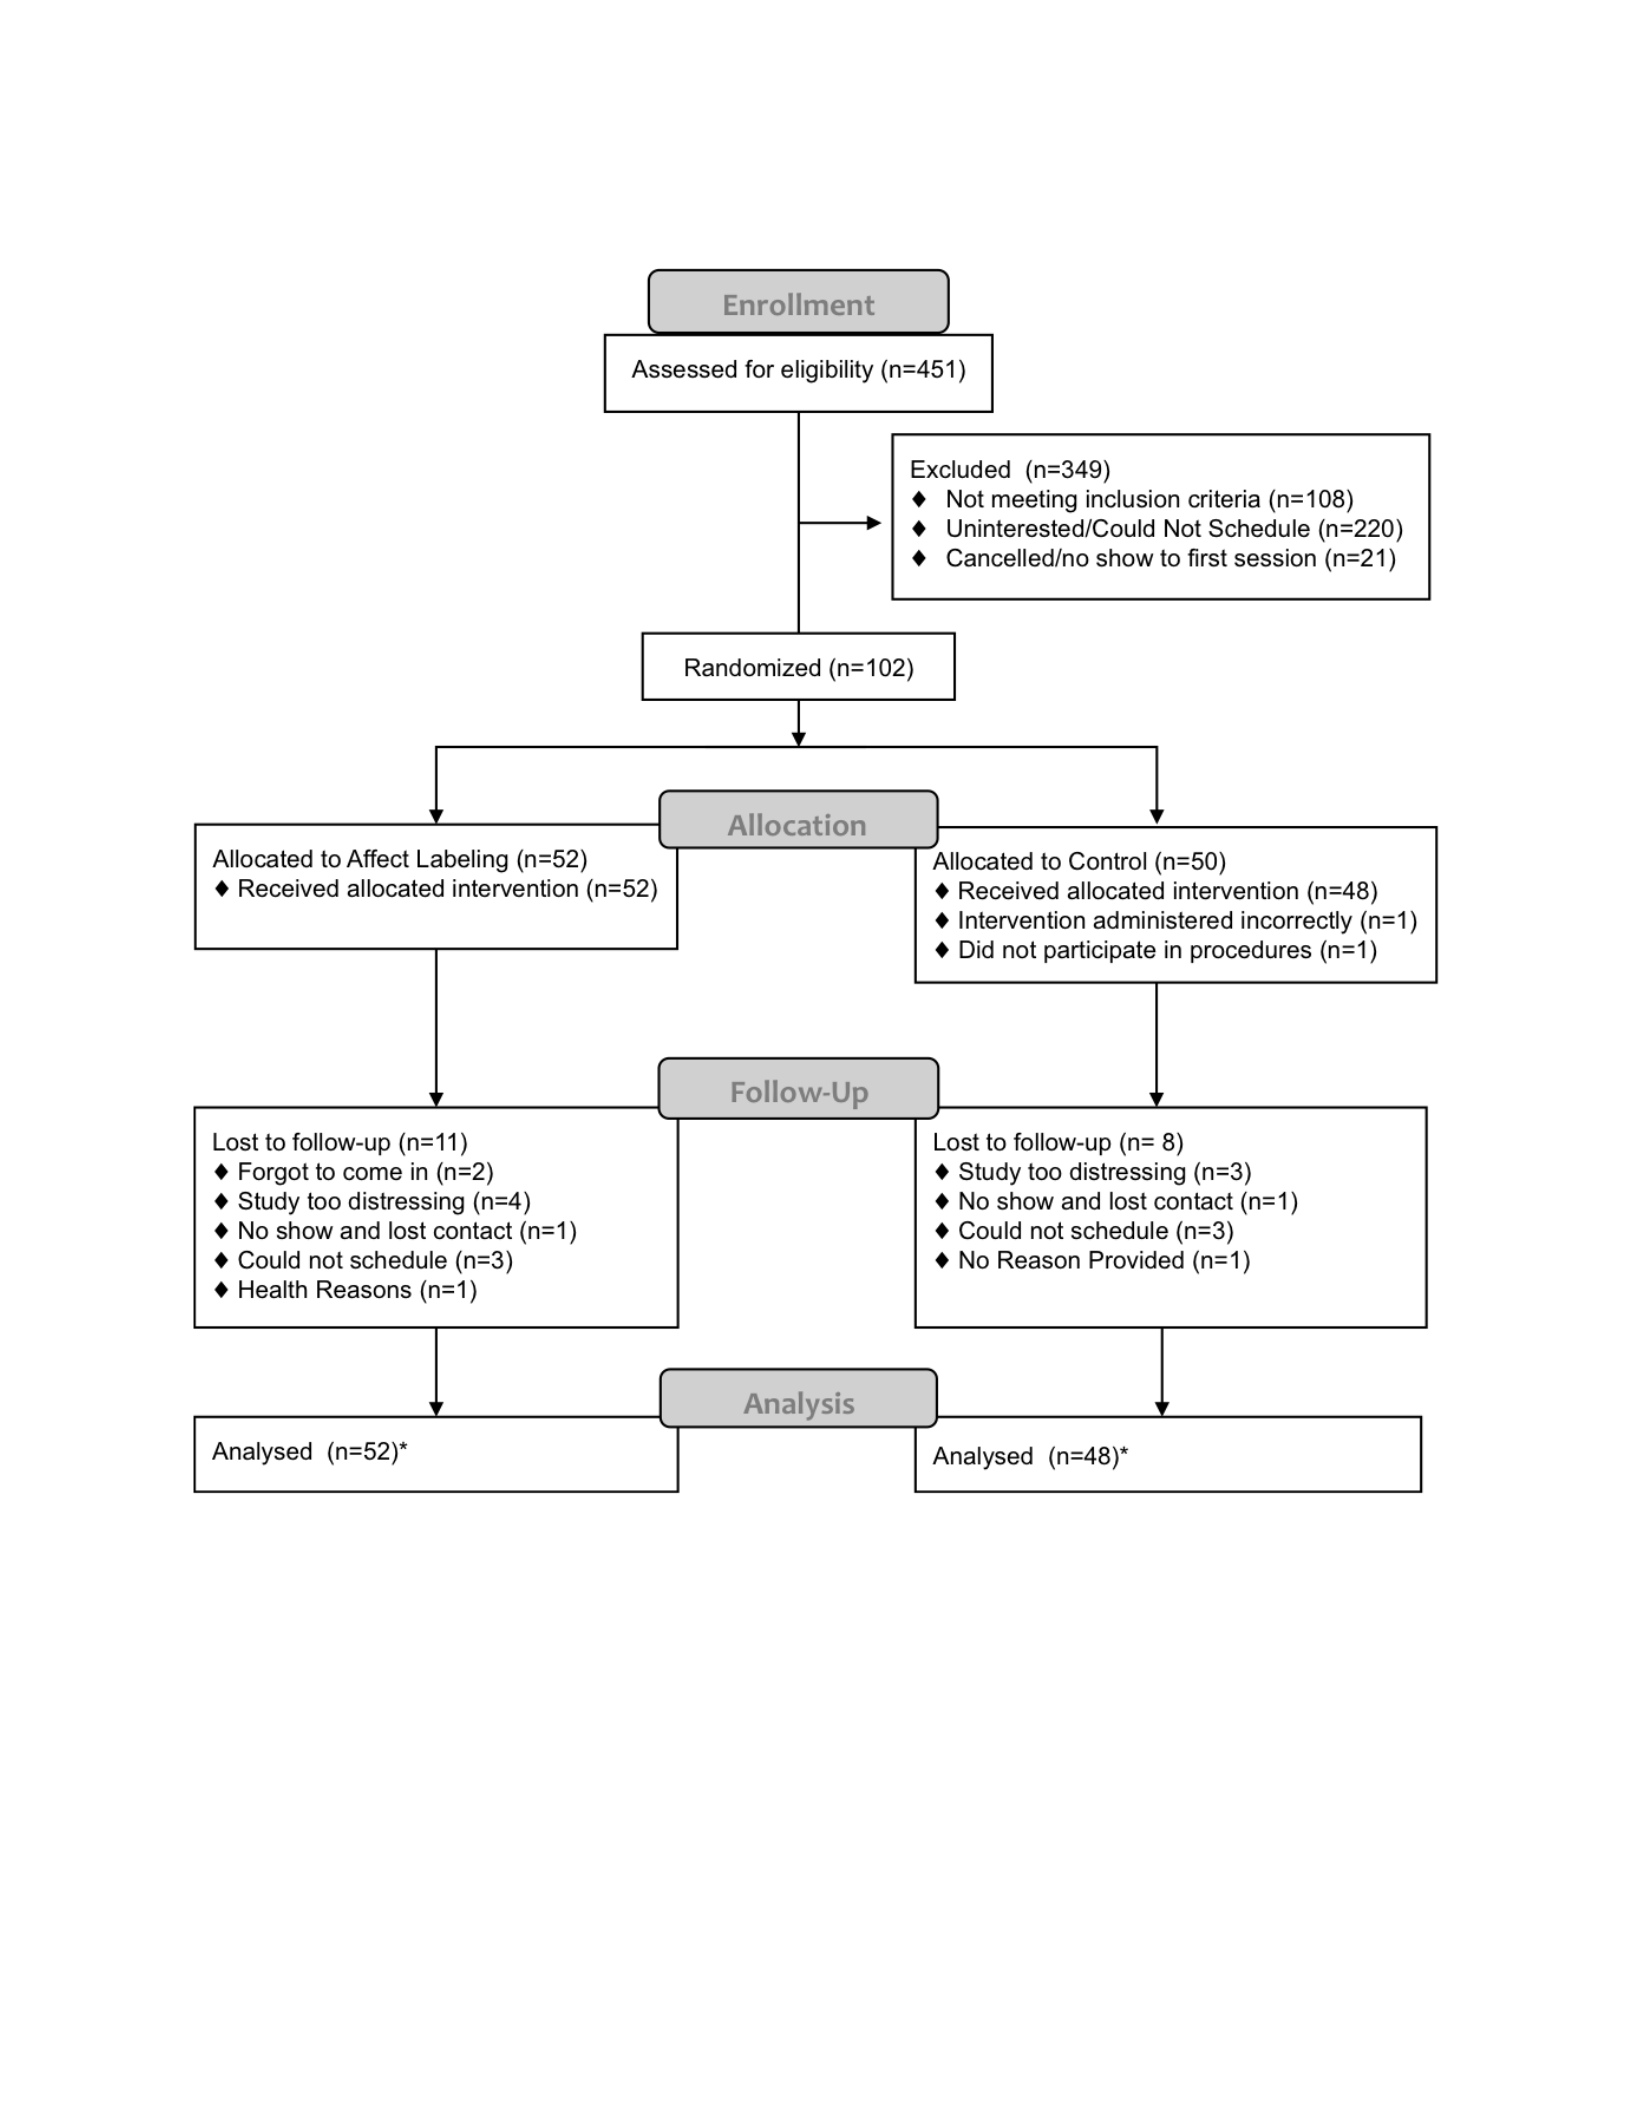
64
Figure 2. Participant Flow Chart
* See Table 2 for additional information regarding missing data
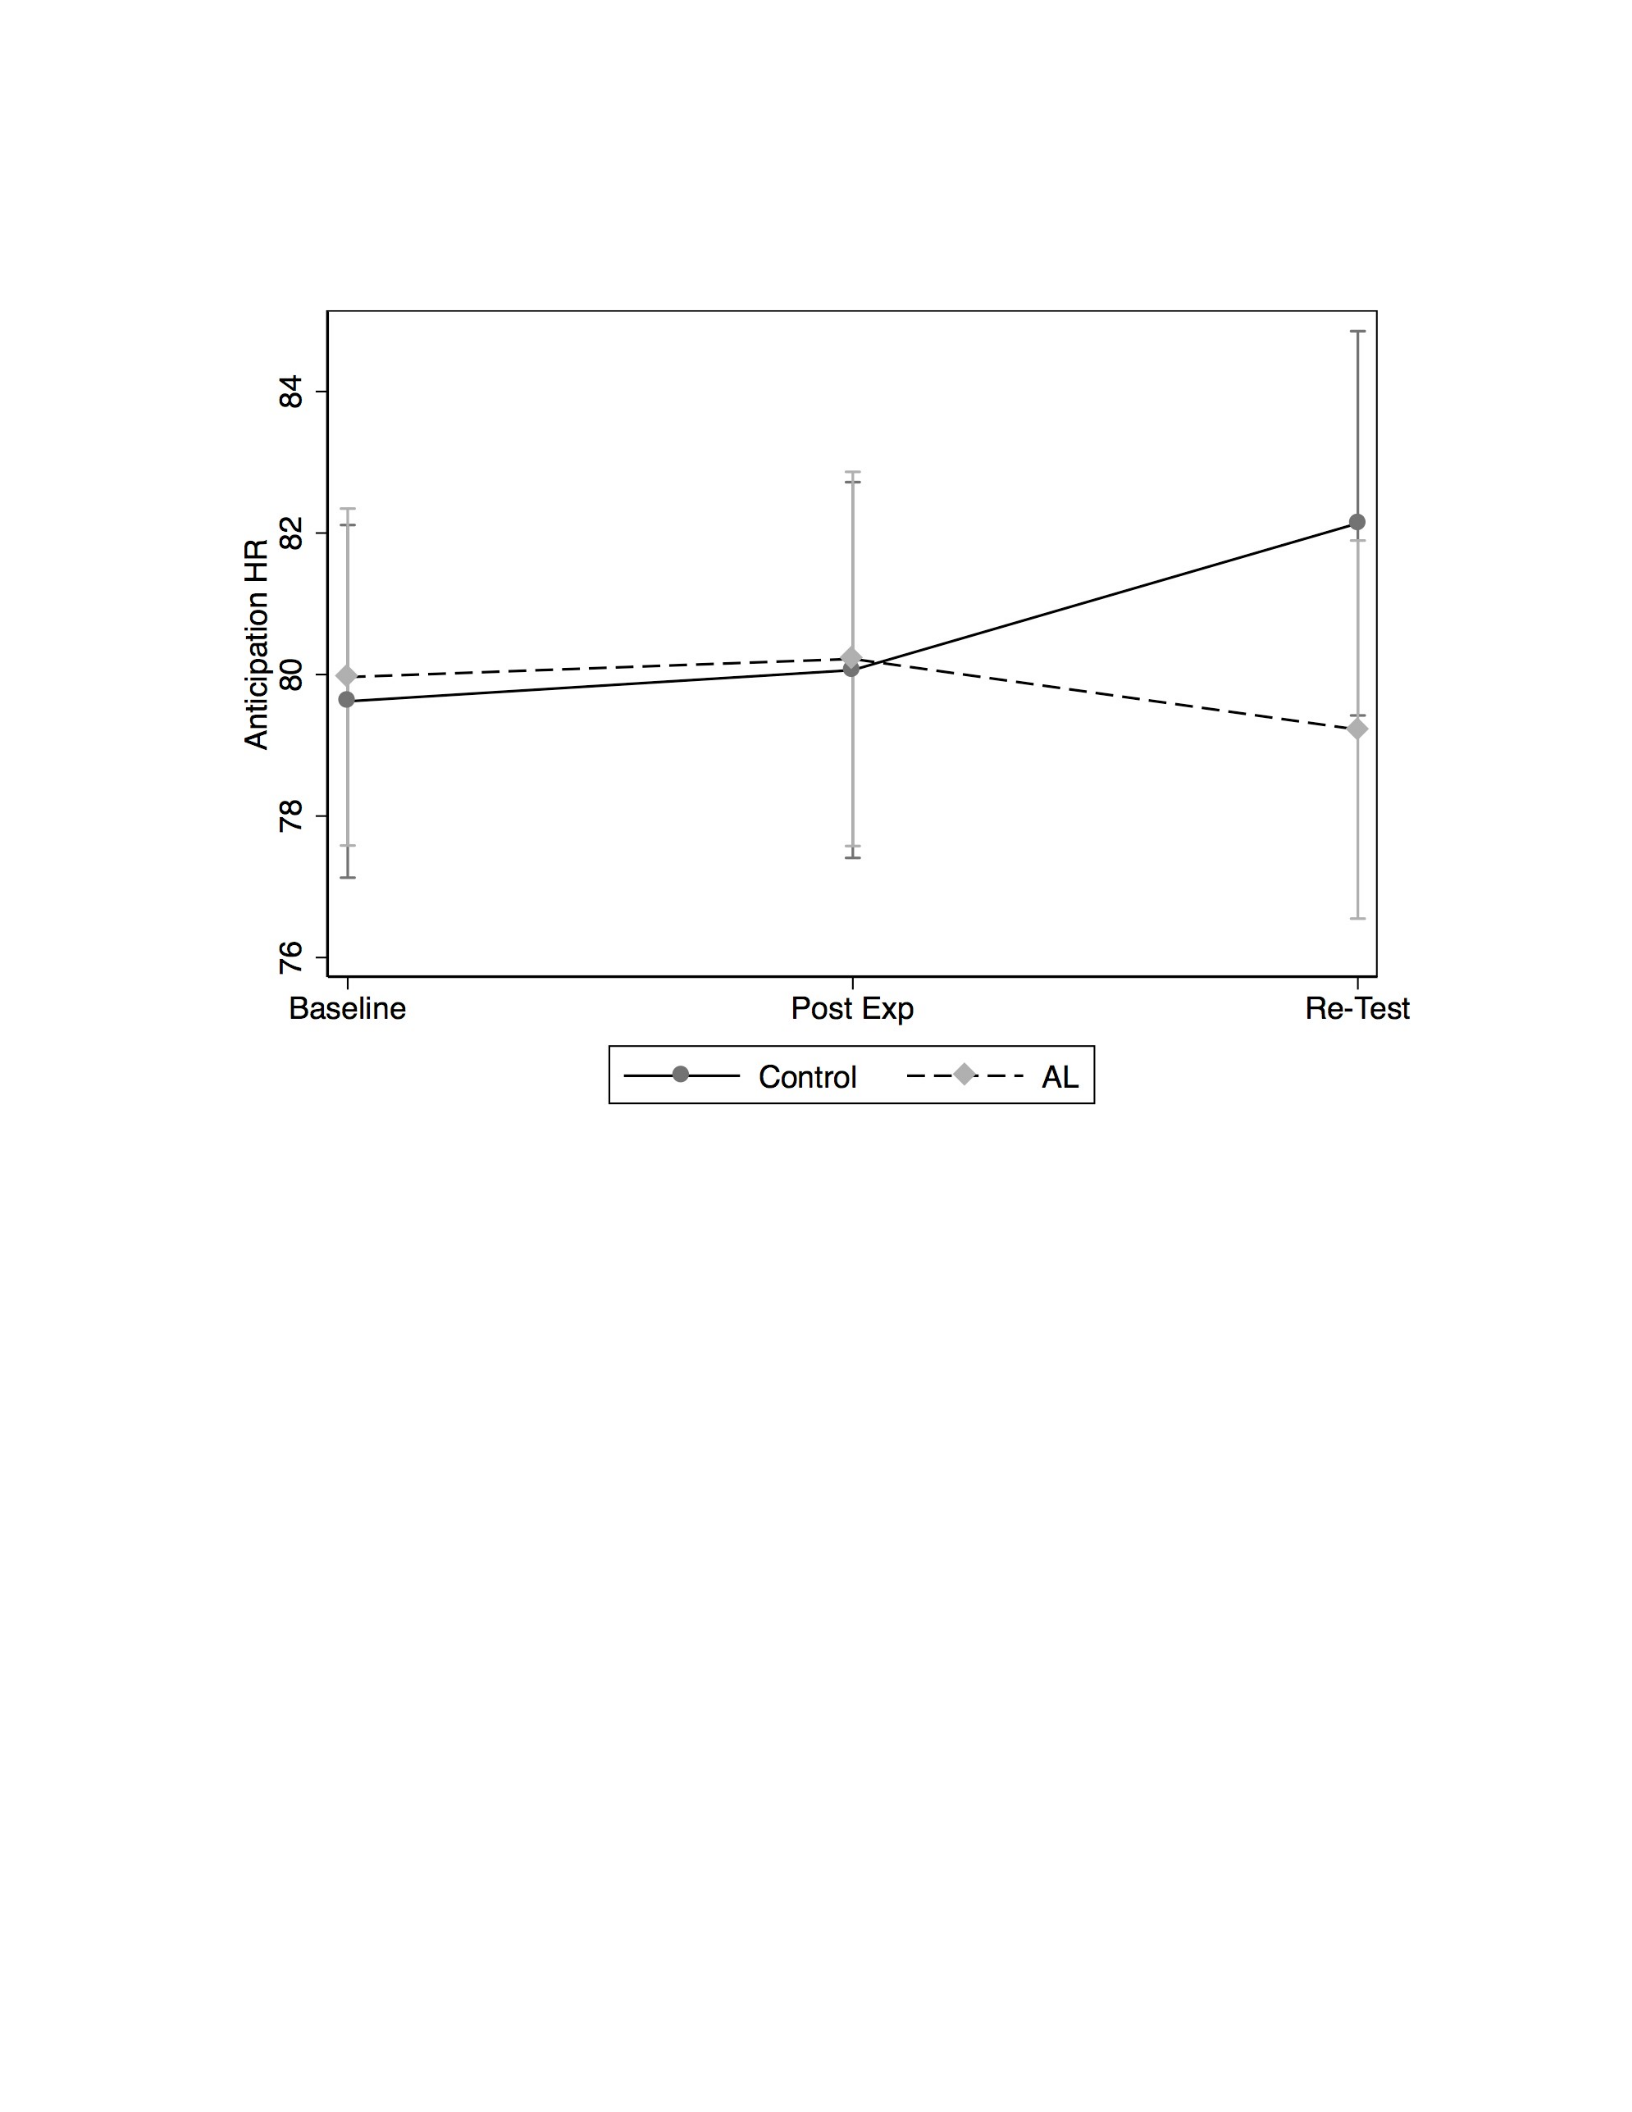
65
Figure 3. Heart Rate Over Time by Group during Anticipation
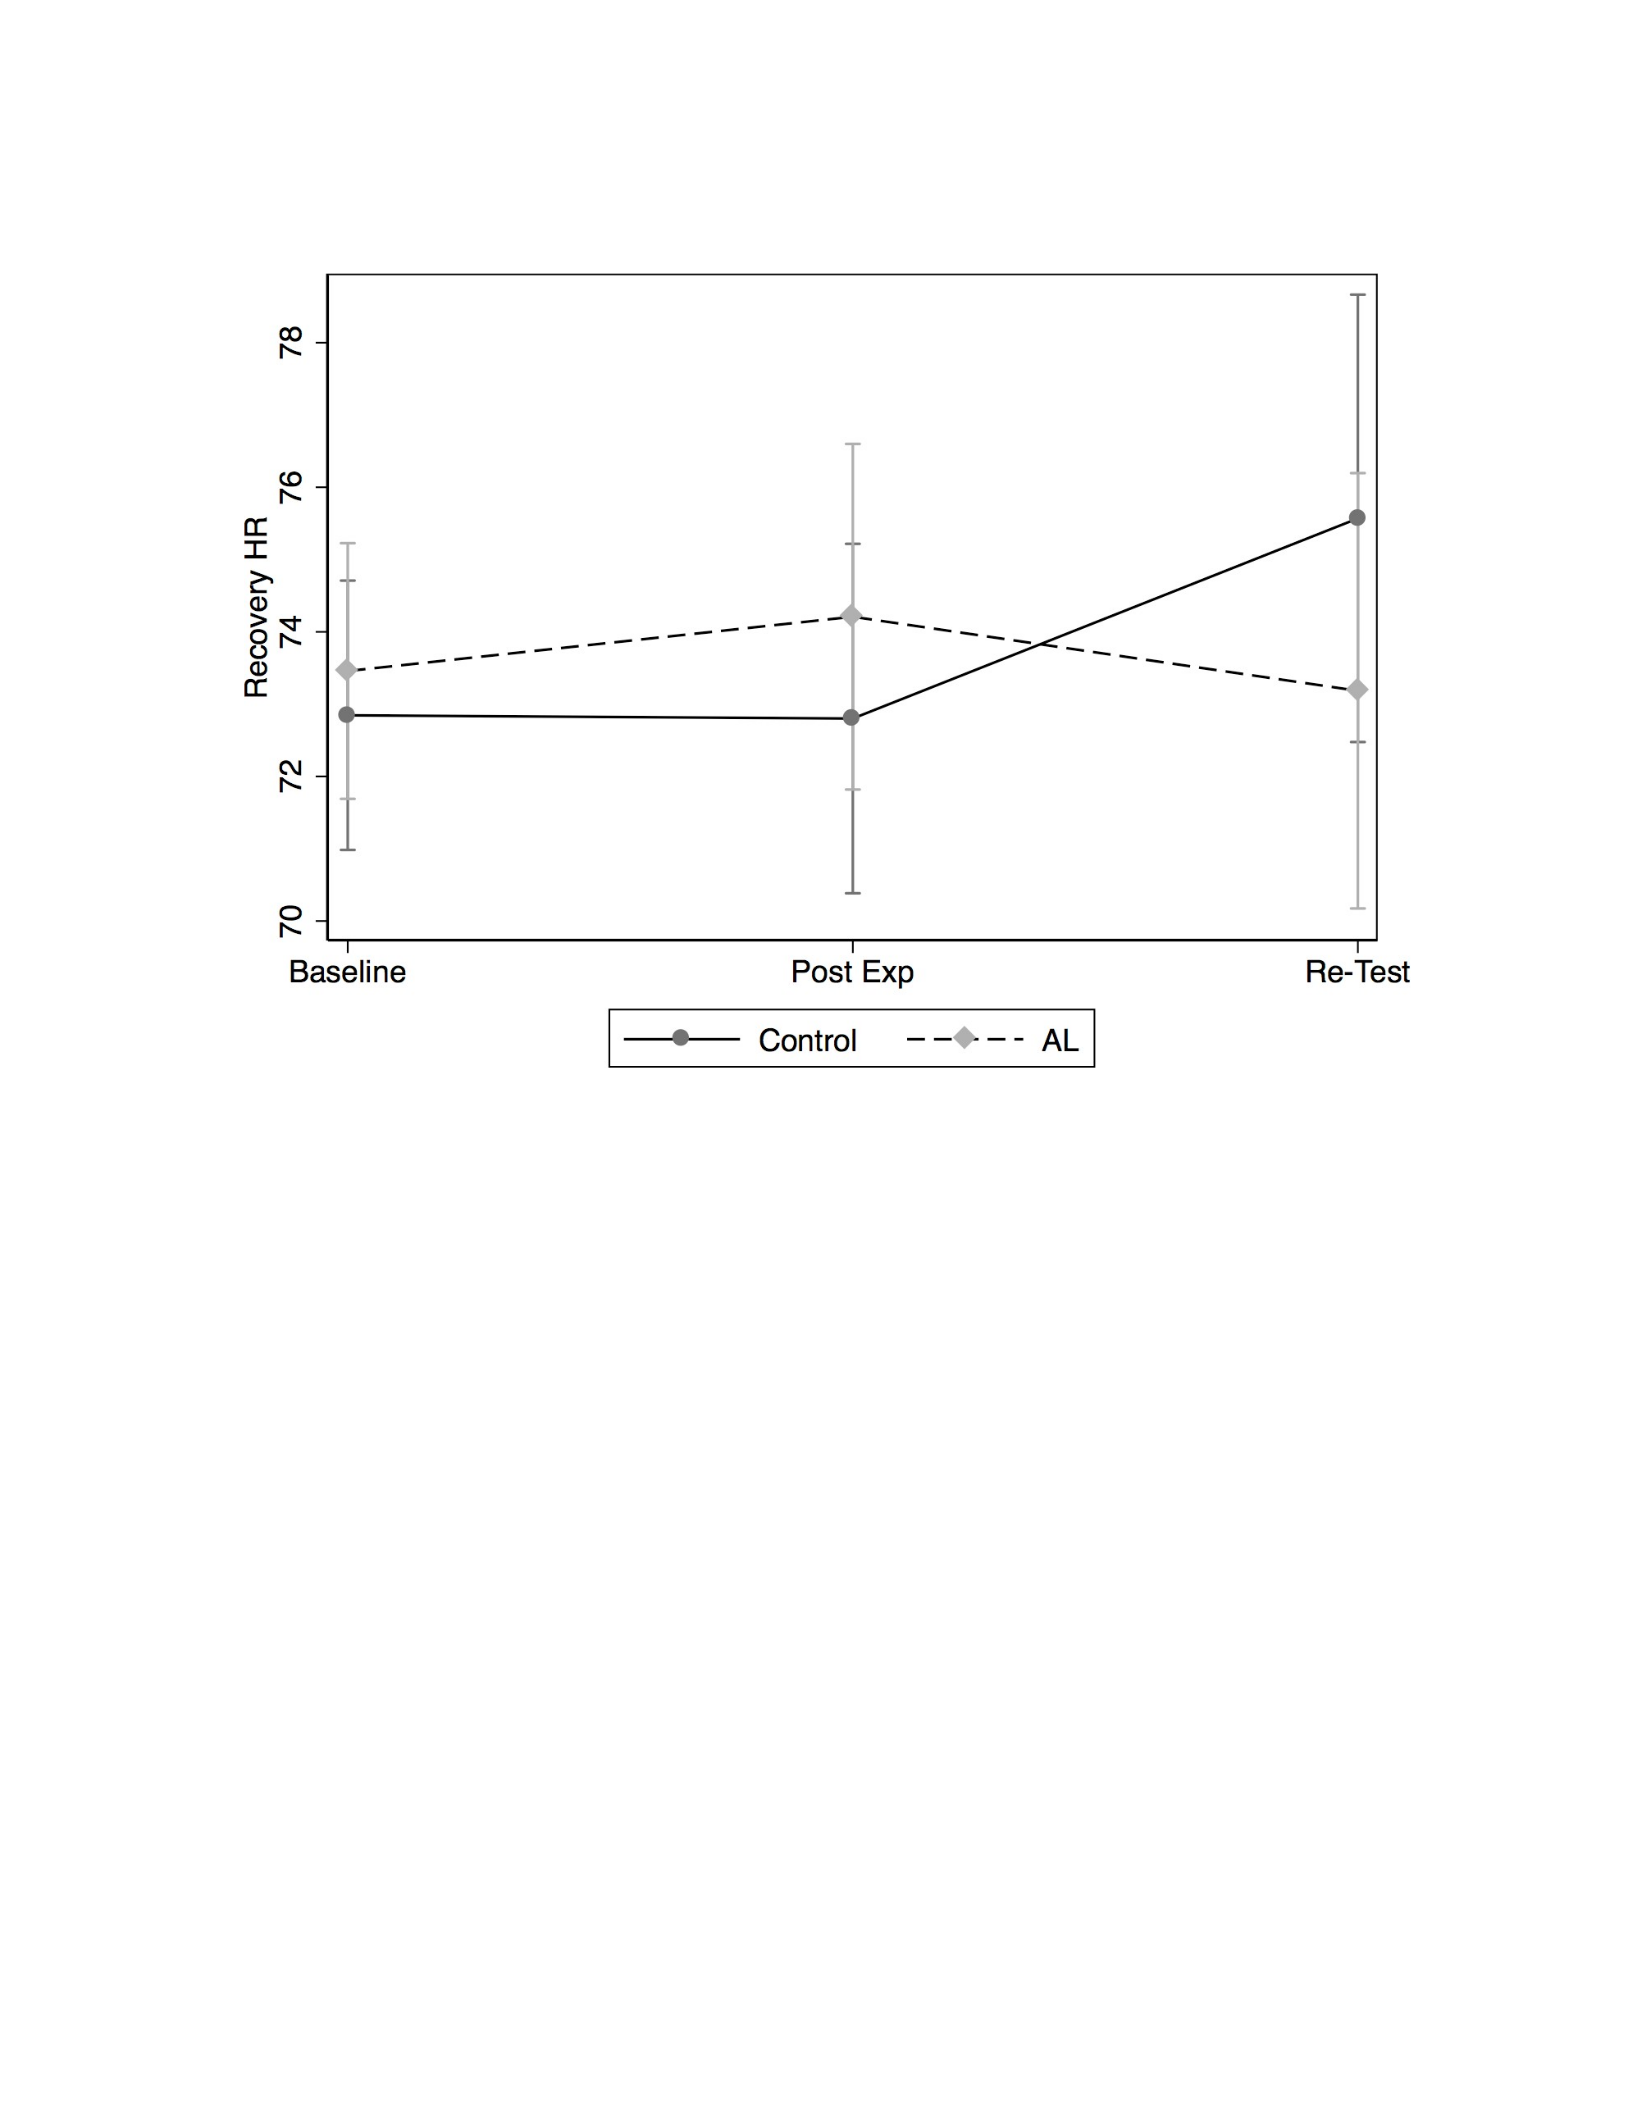
66
Figure 4. Heart Rate During Recovery Over Time by Group
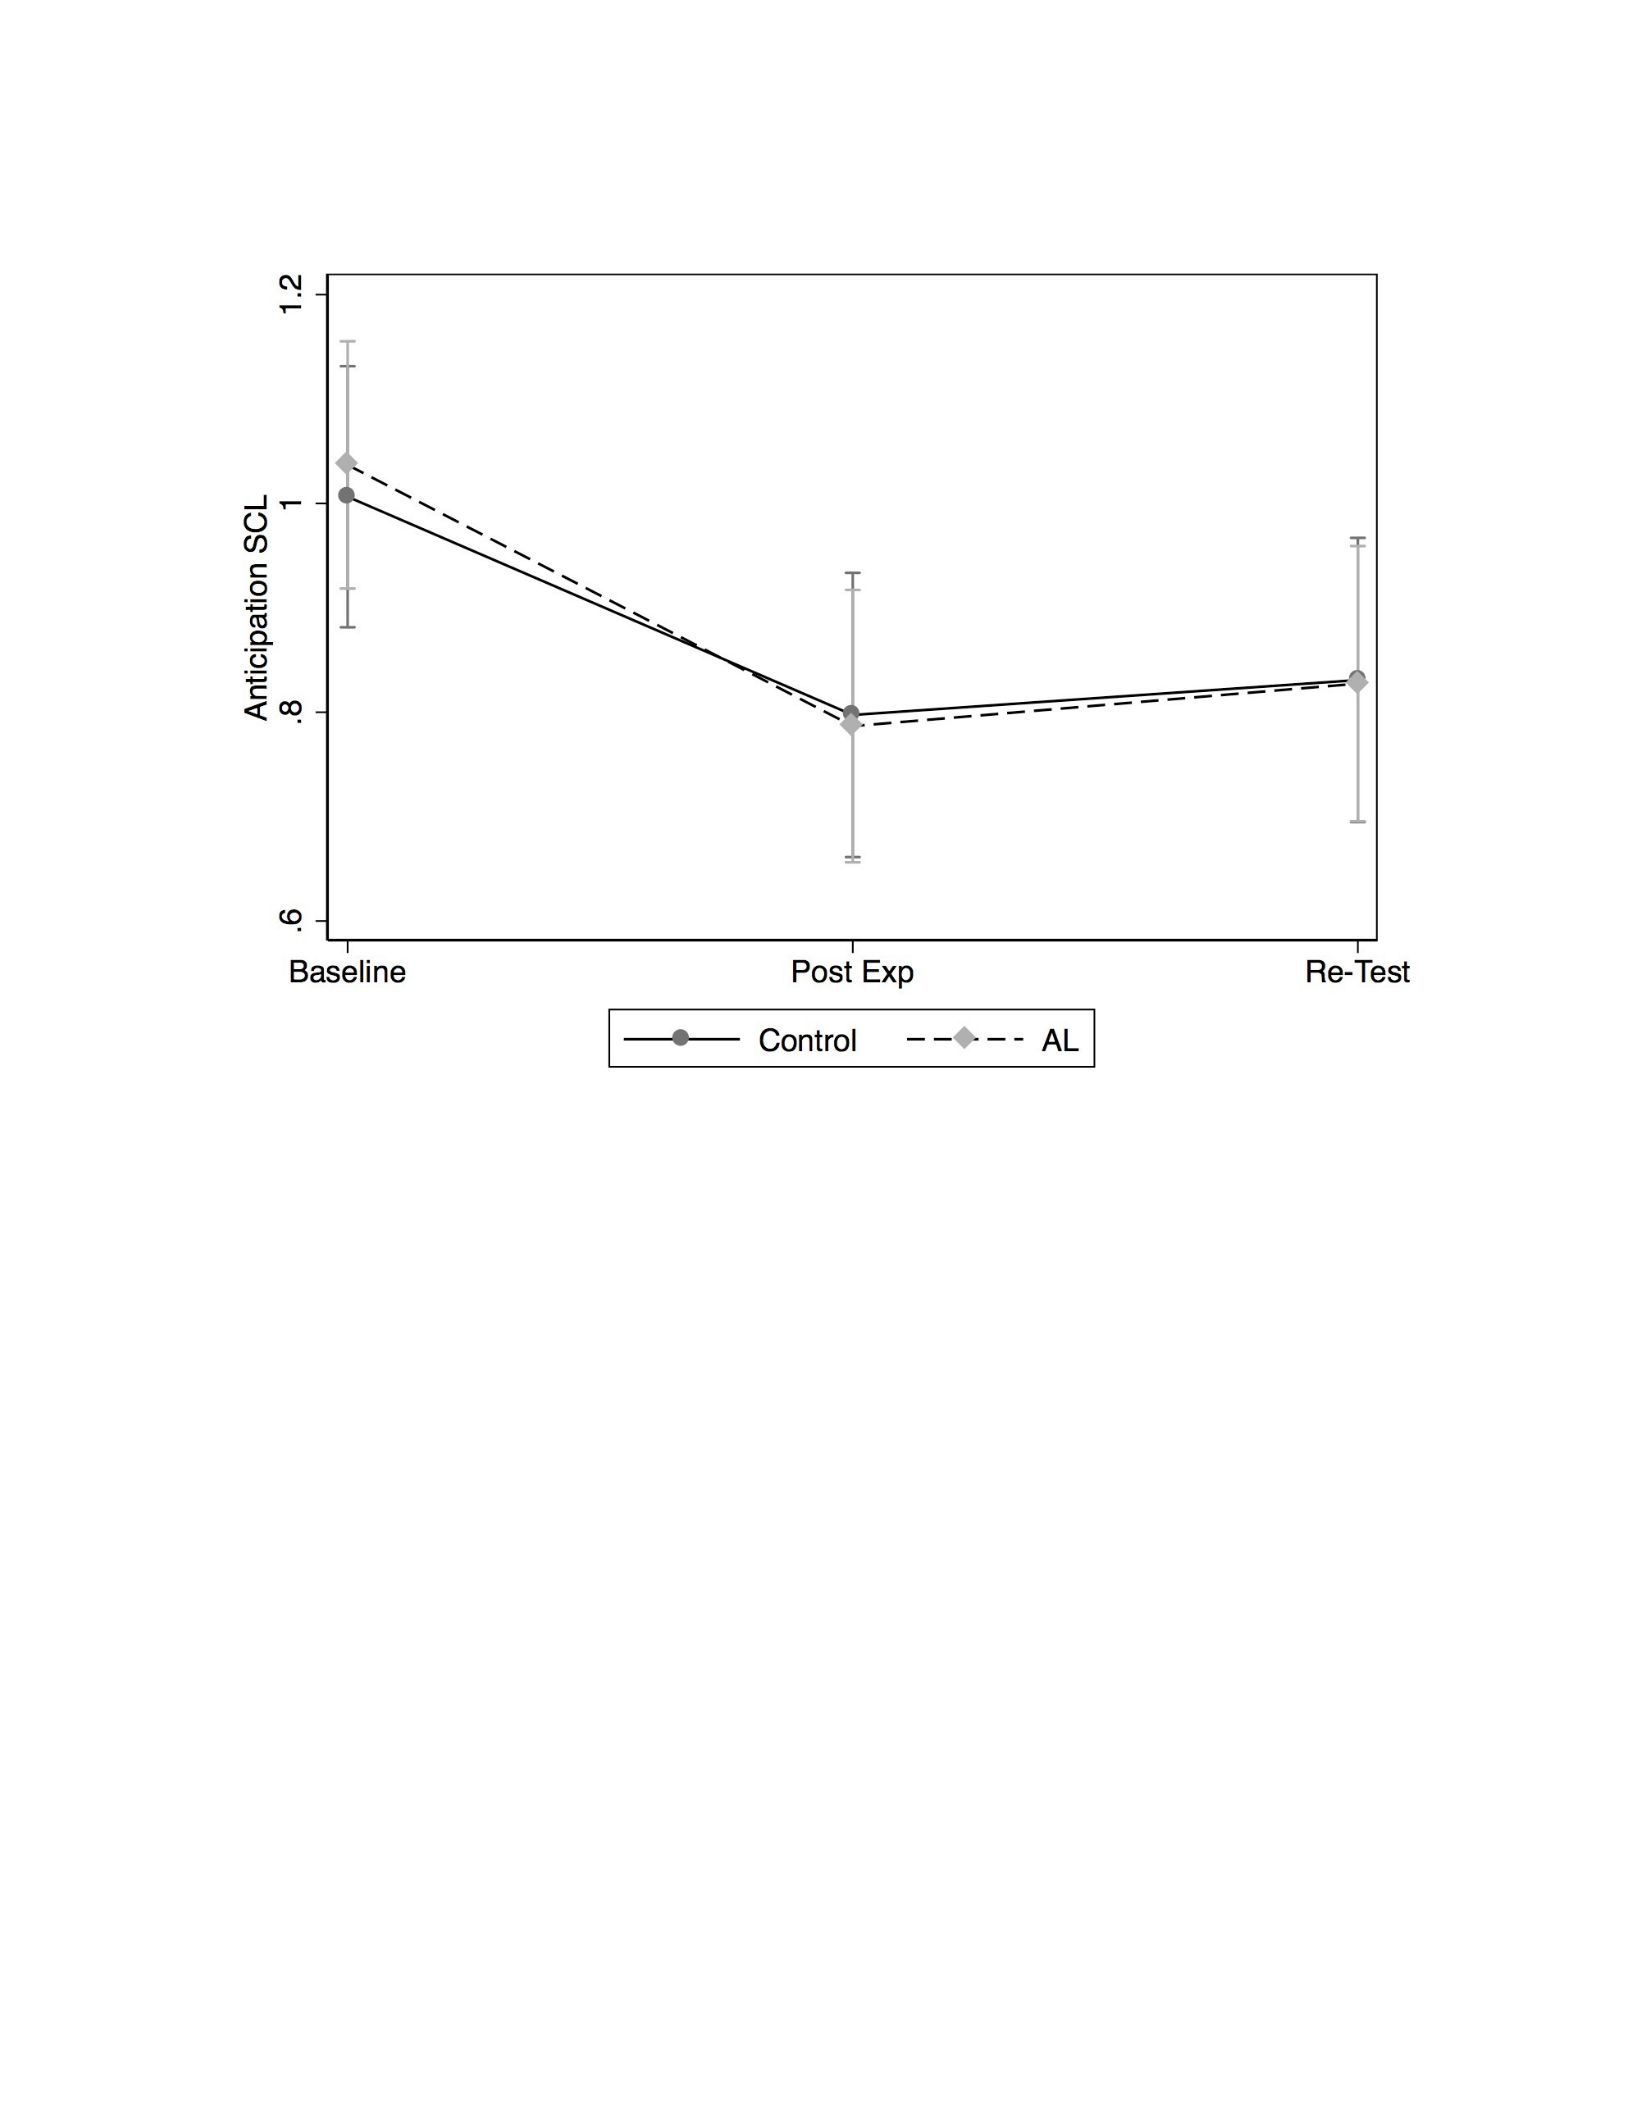
67
Figure 5. Skin Conductance Level During Anticipation Over Time by Group
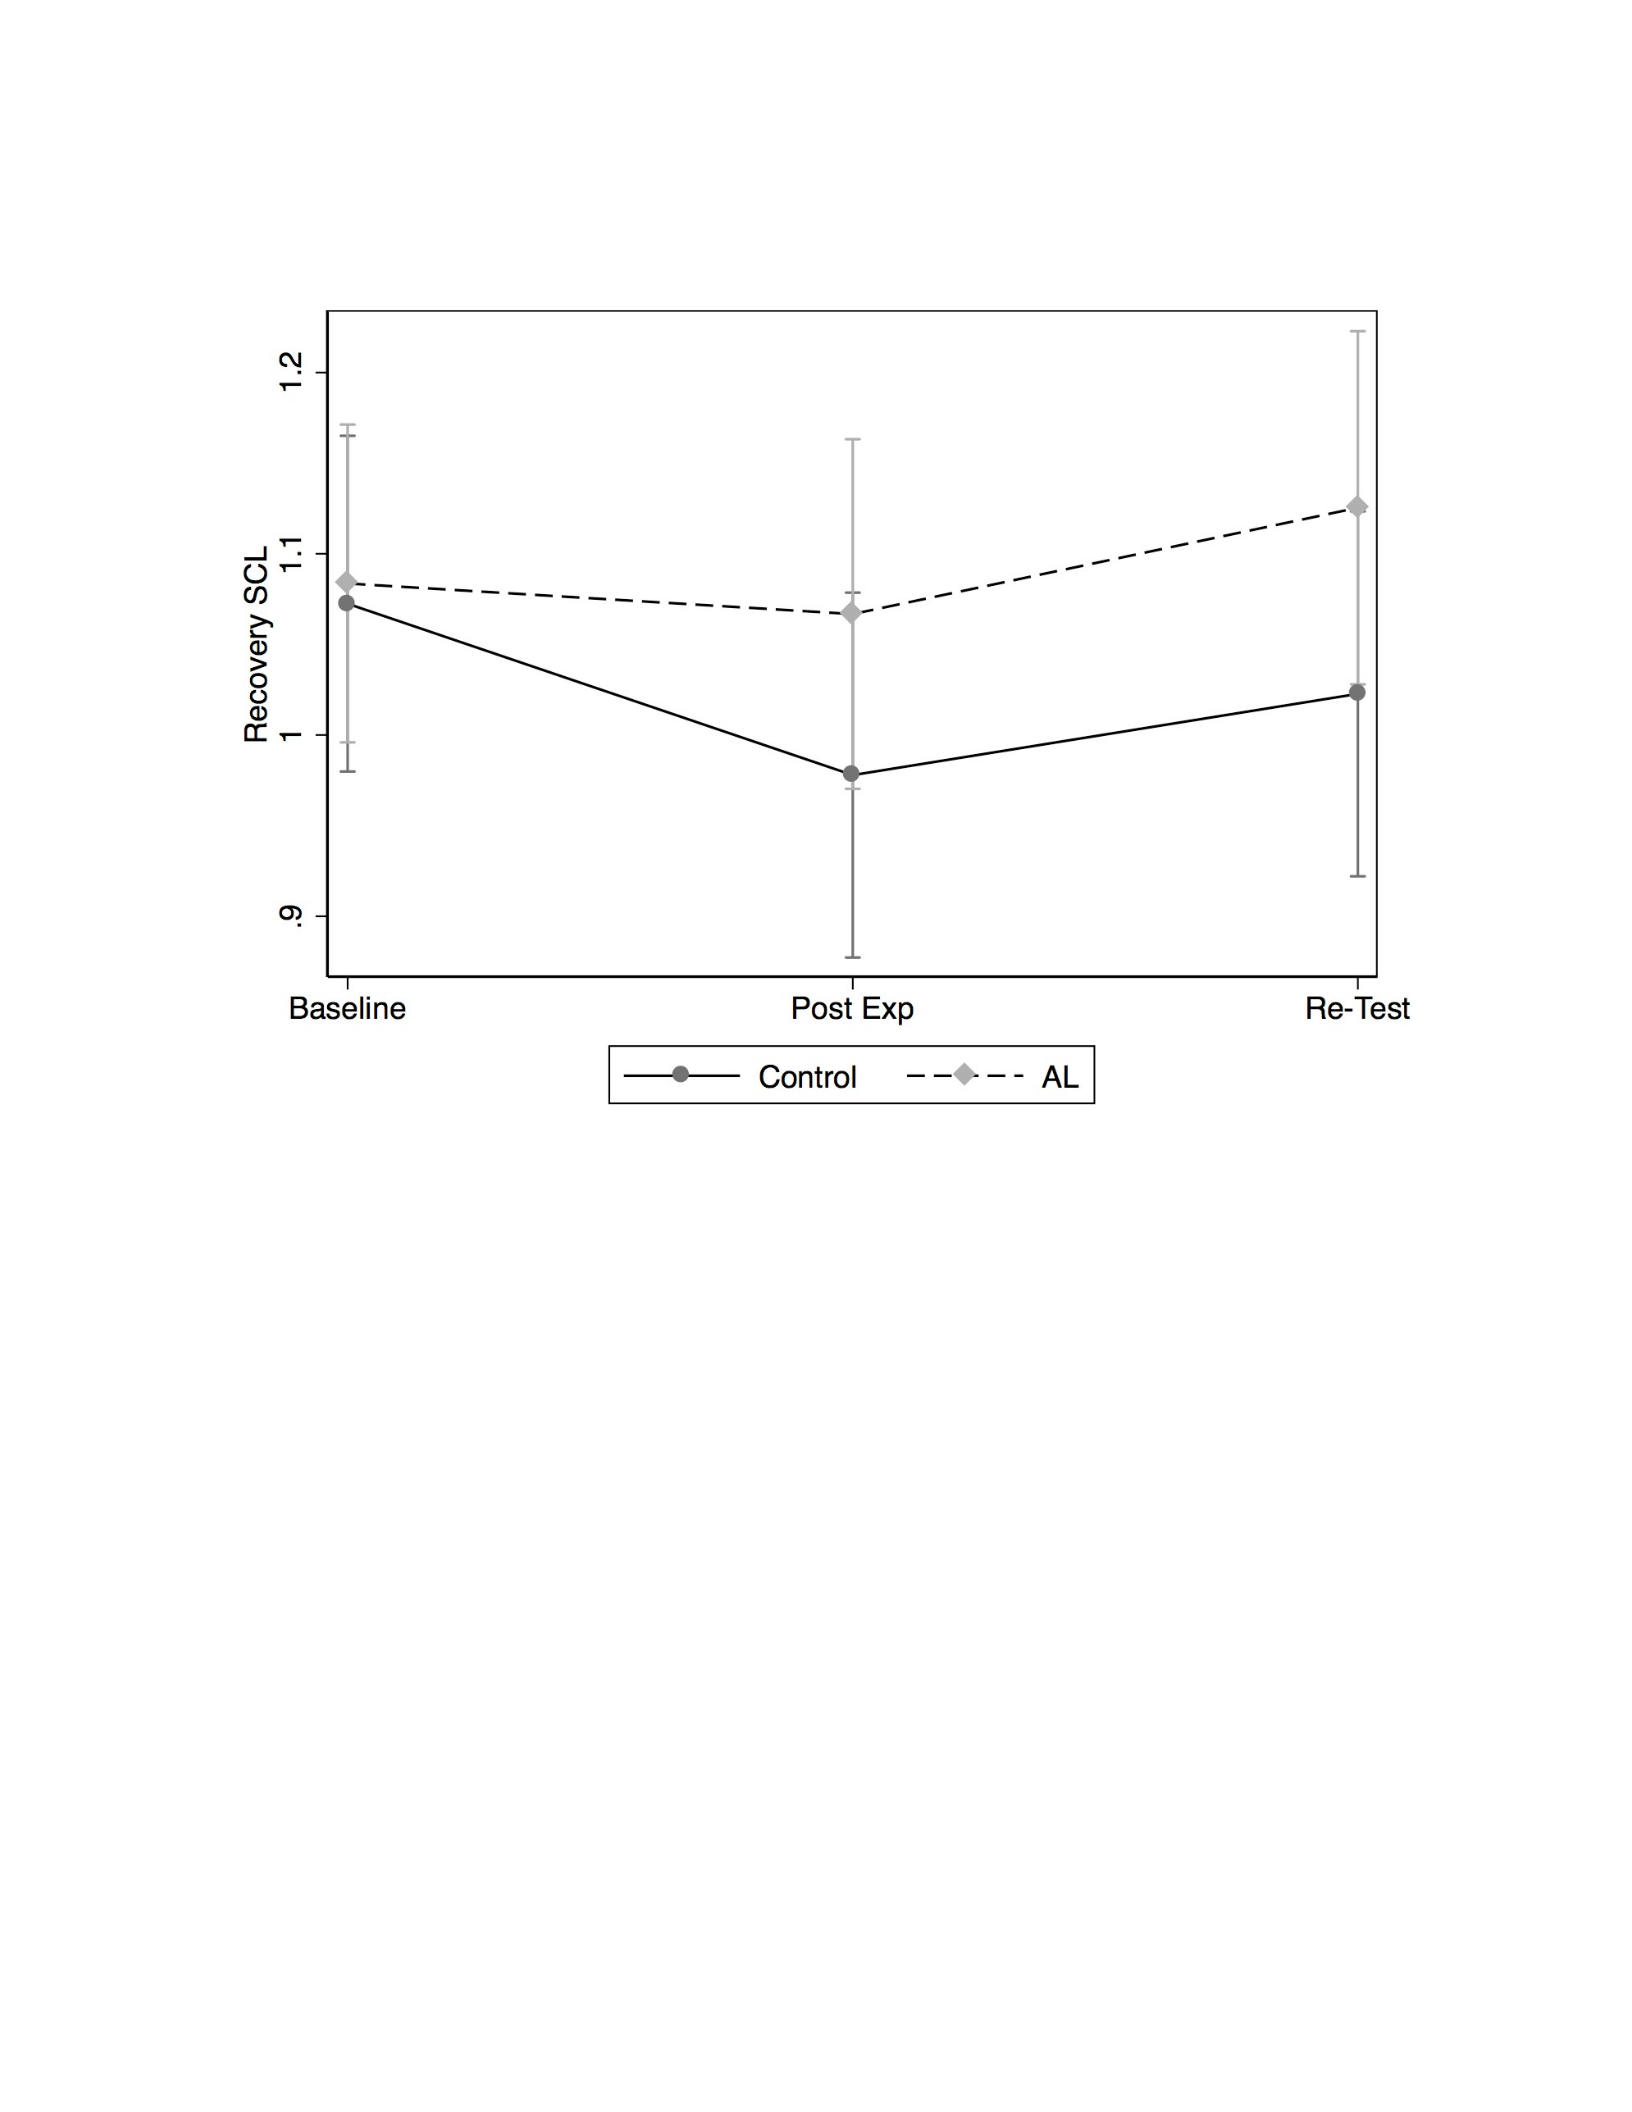
68
Figure 6. Skin Conductance Level During Recovery Over Time by Group
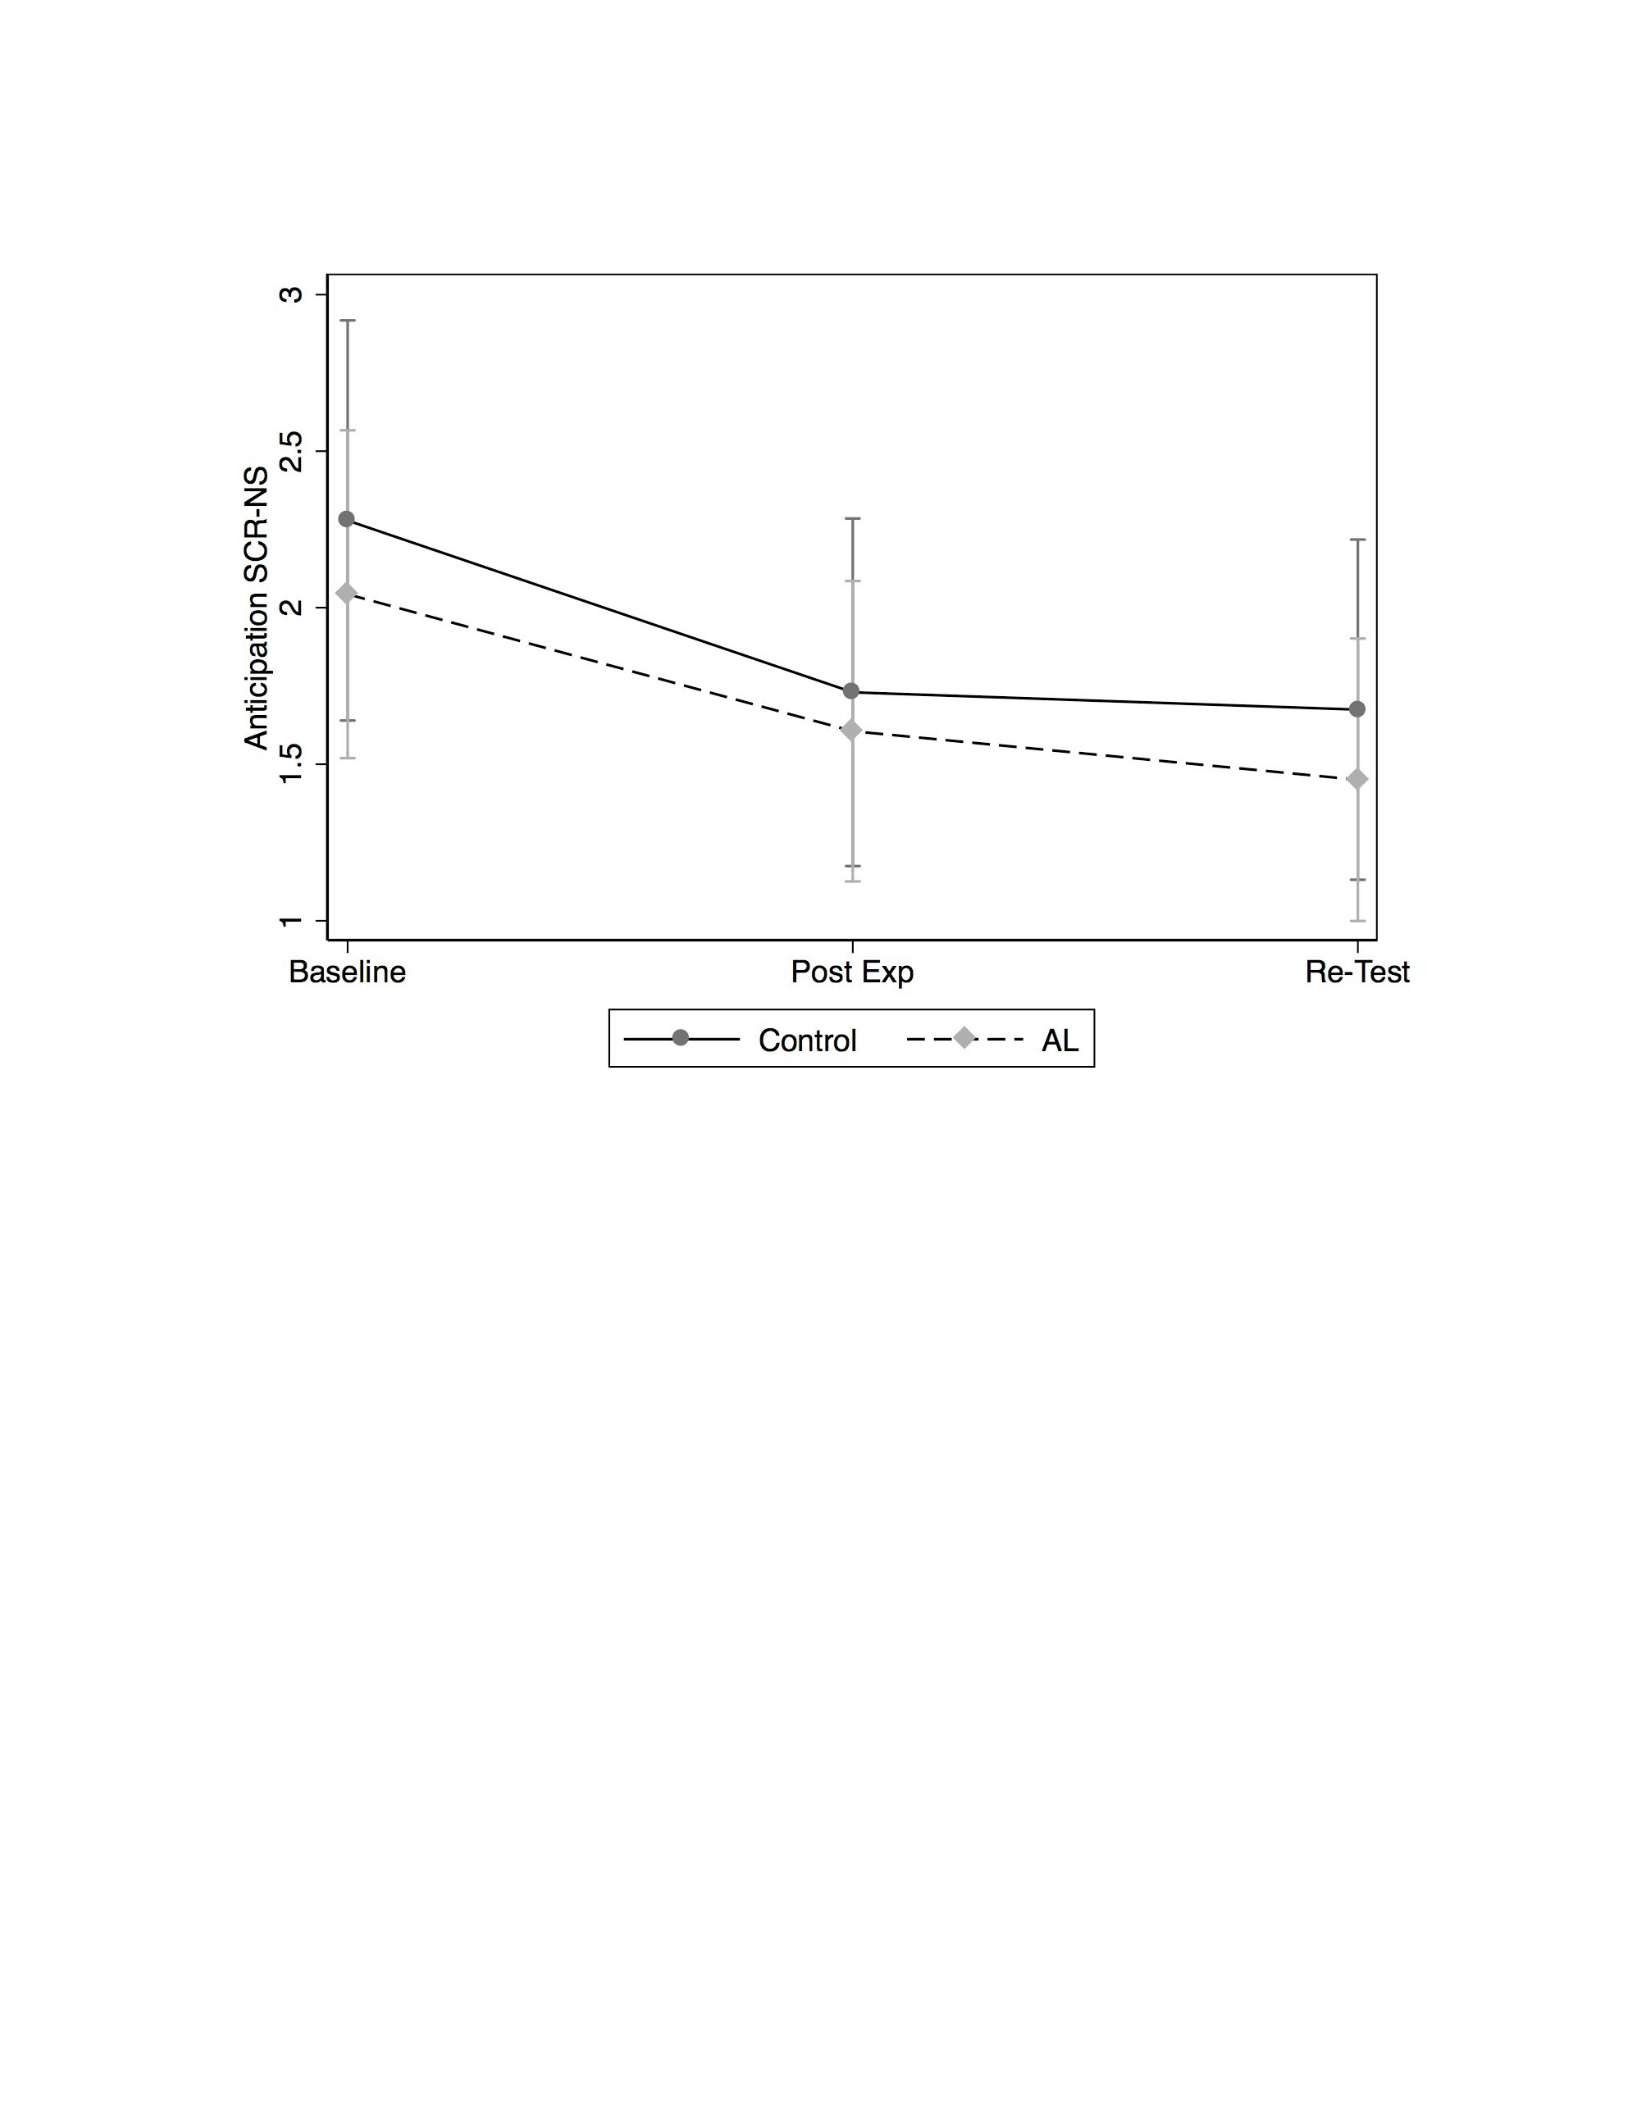
69
Figure 7. Non-Specific Skin Conductance Response During Anticipation Over Time by Group
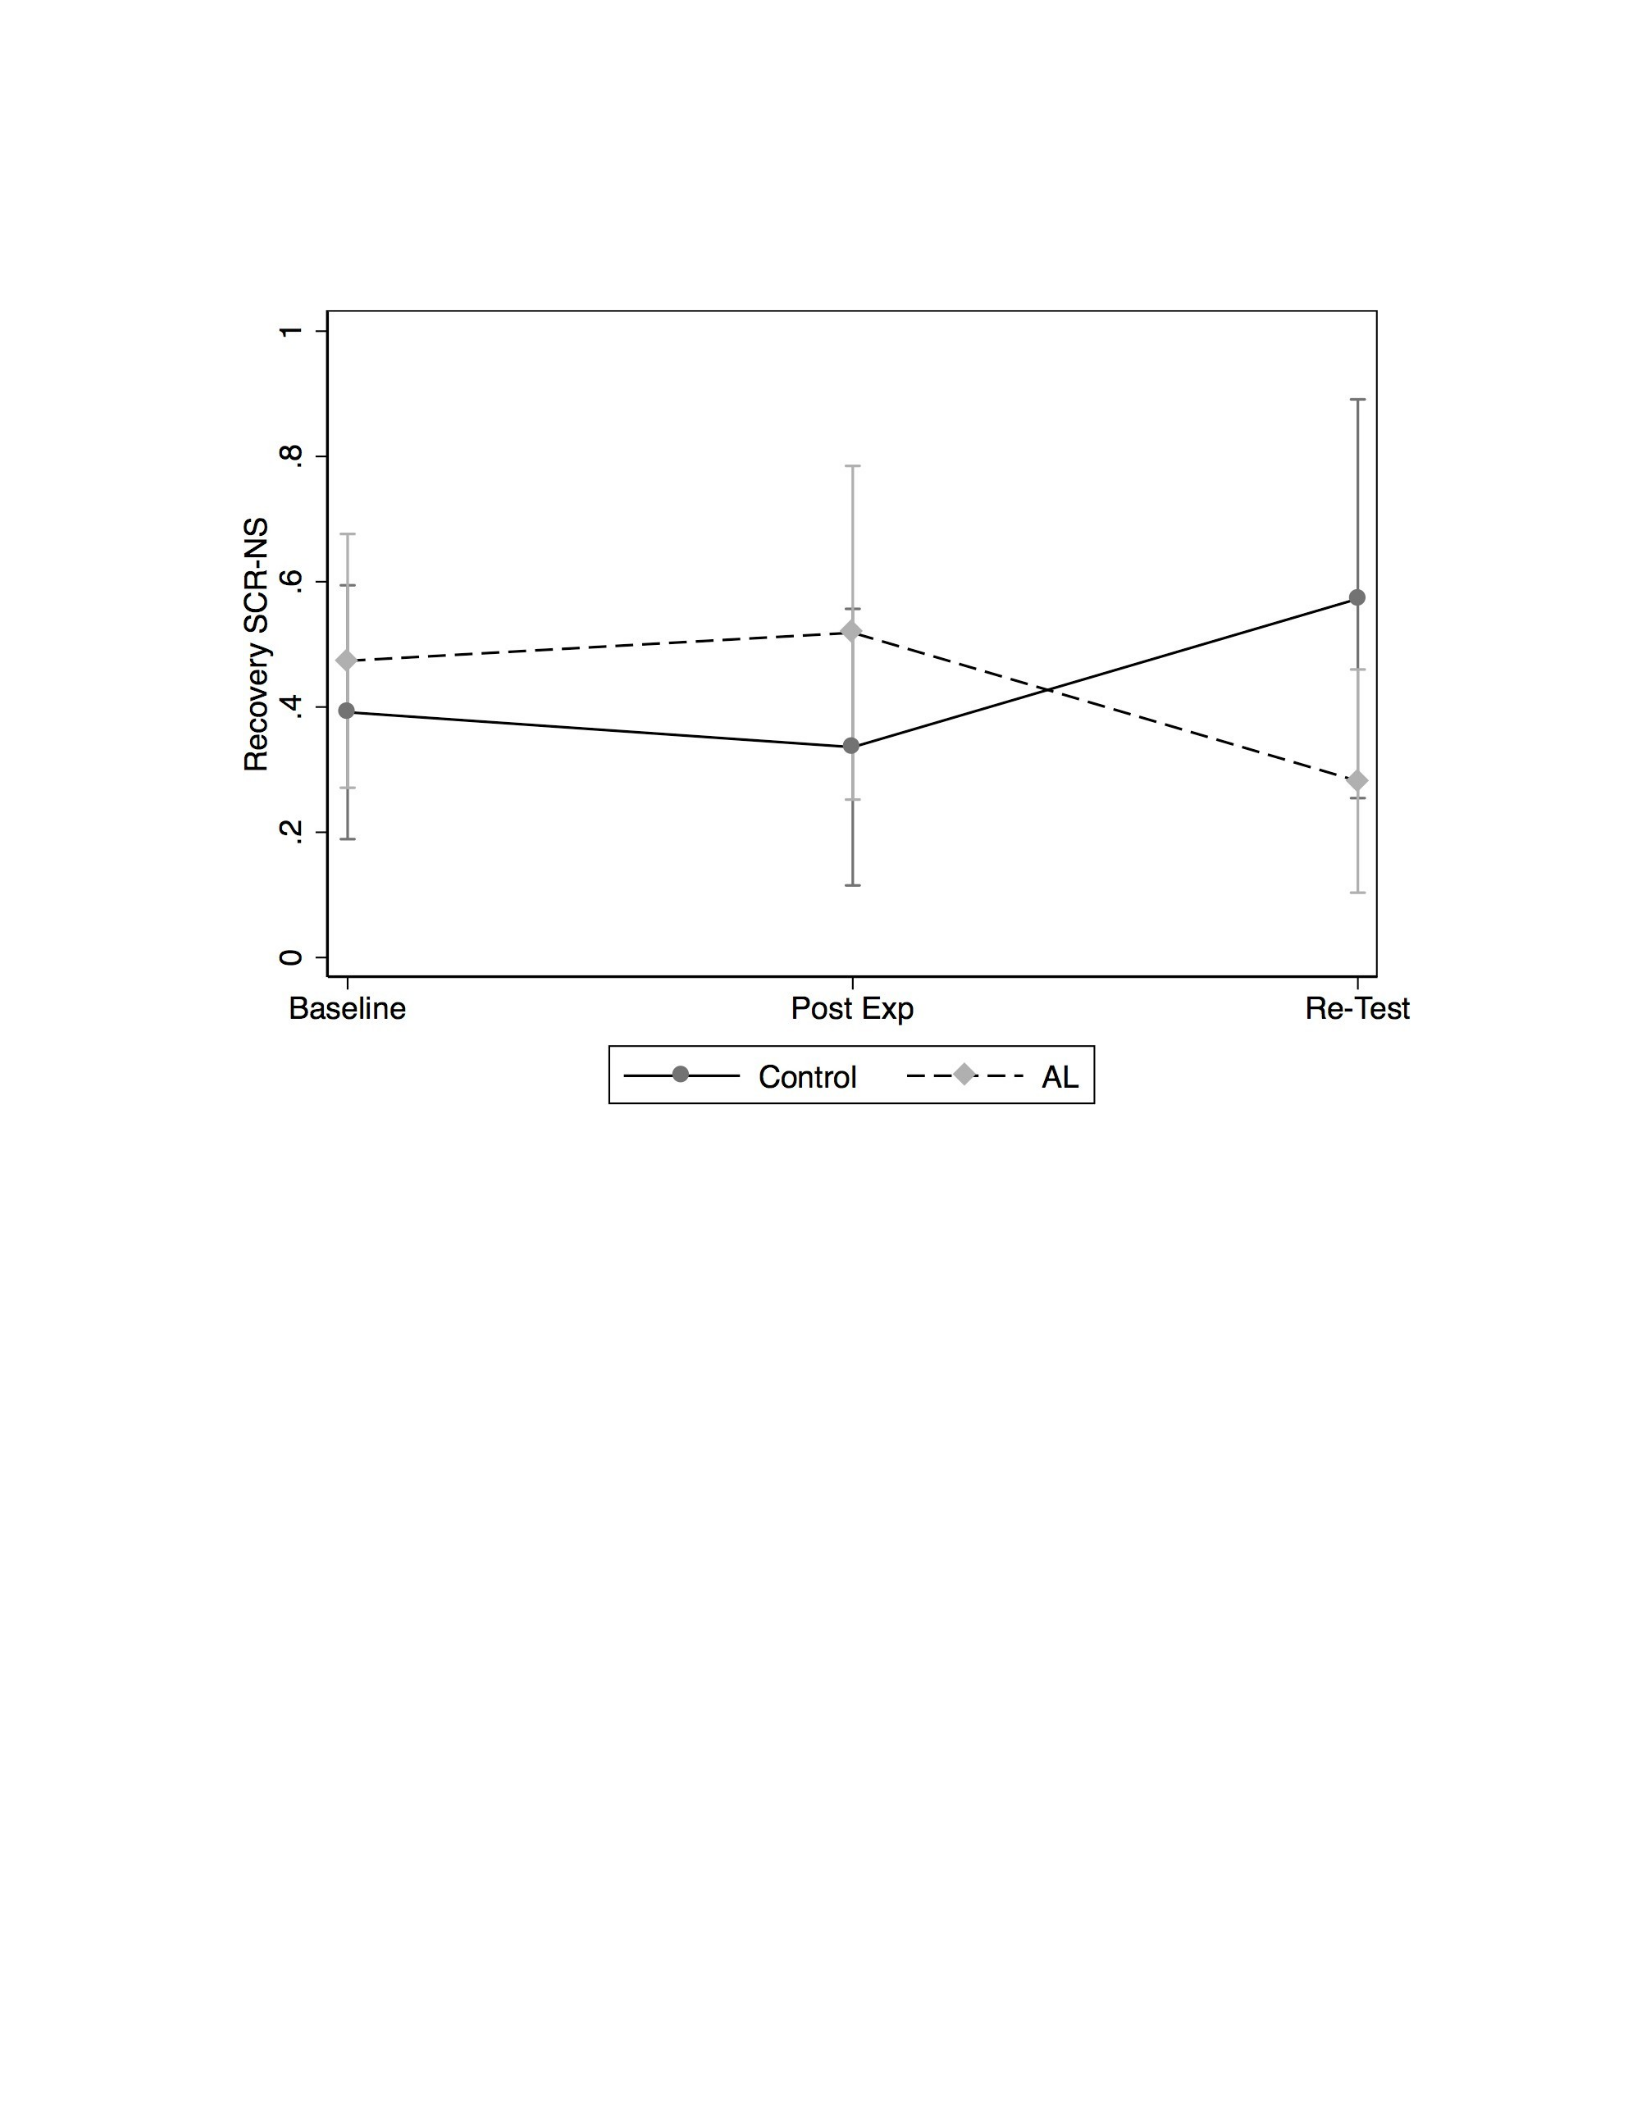
70
Figure 8. Non-Specific Skin Conductance Response During Recovery Over Time by Group
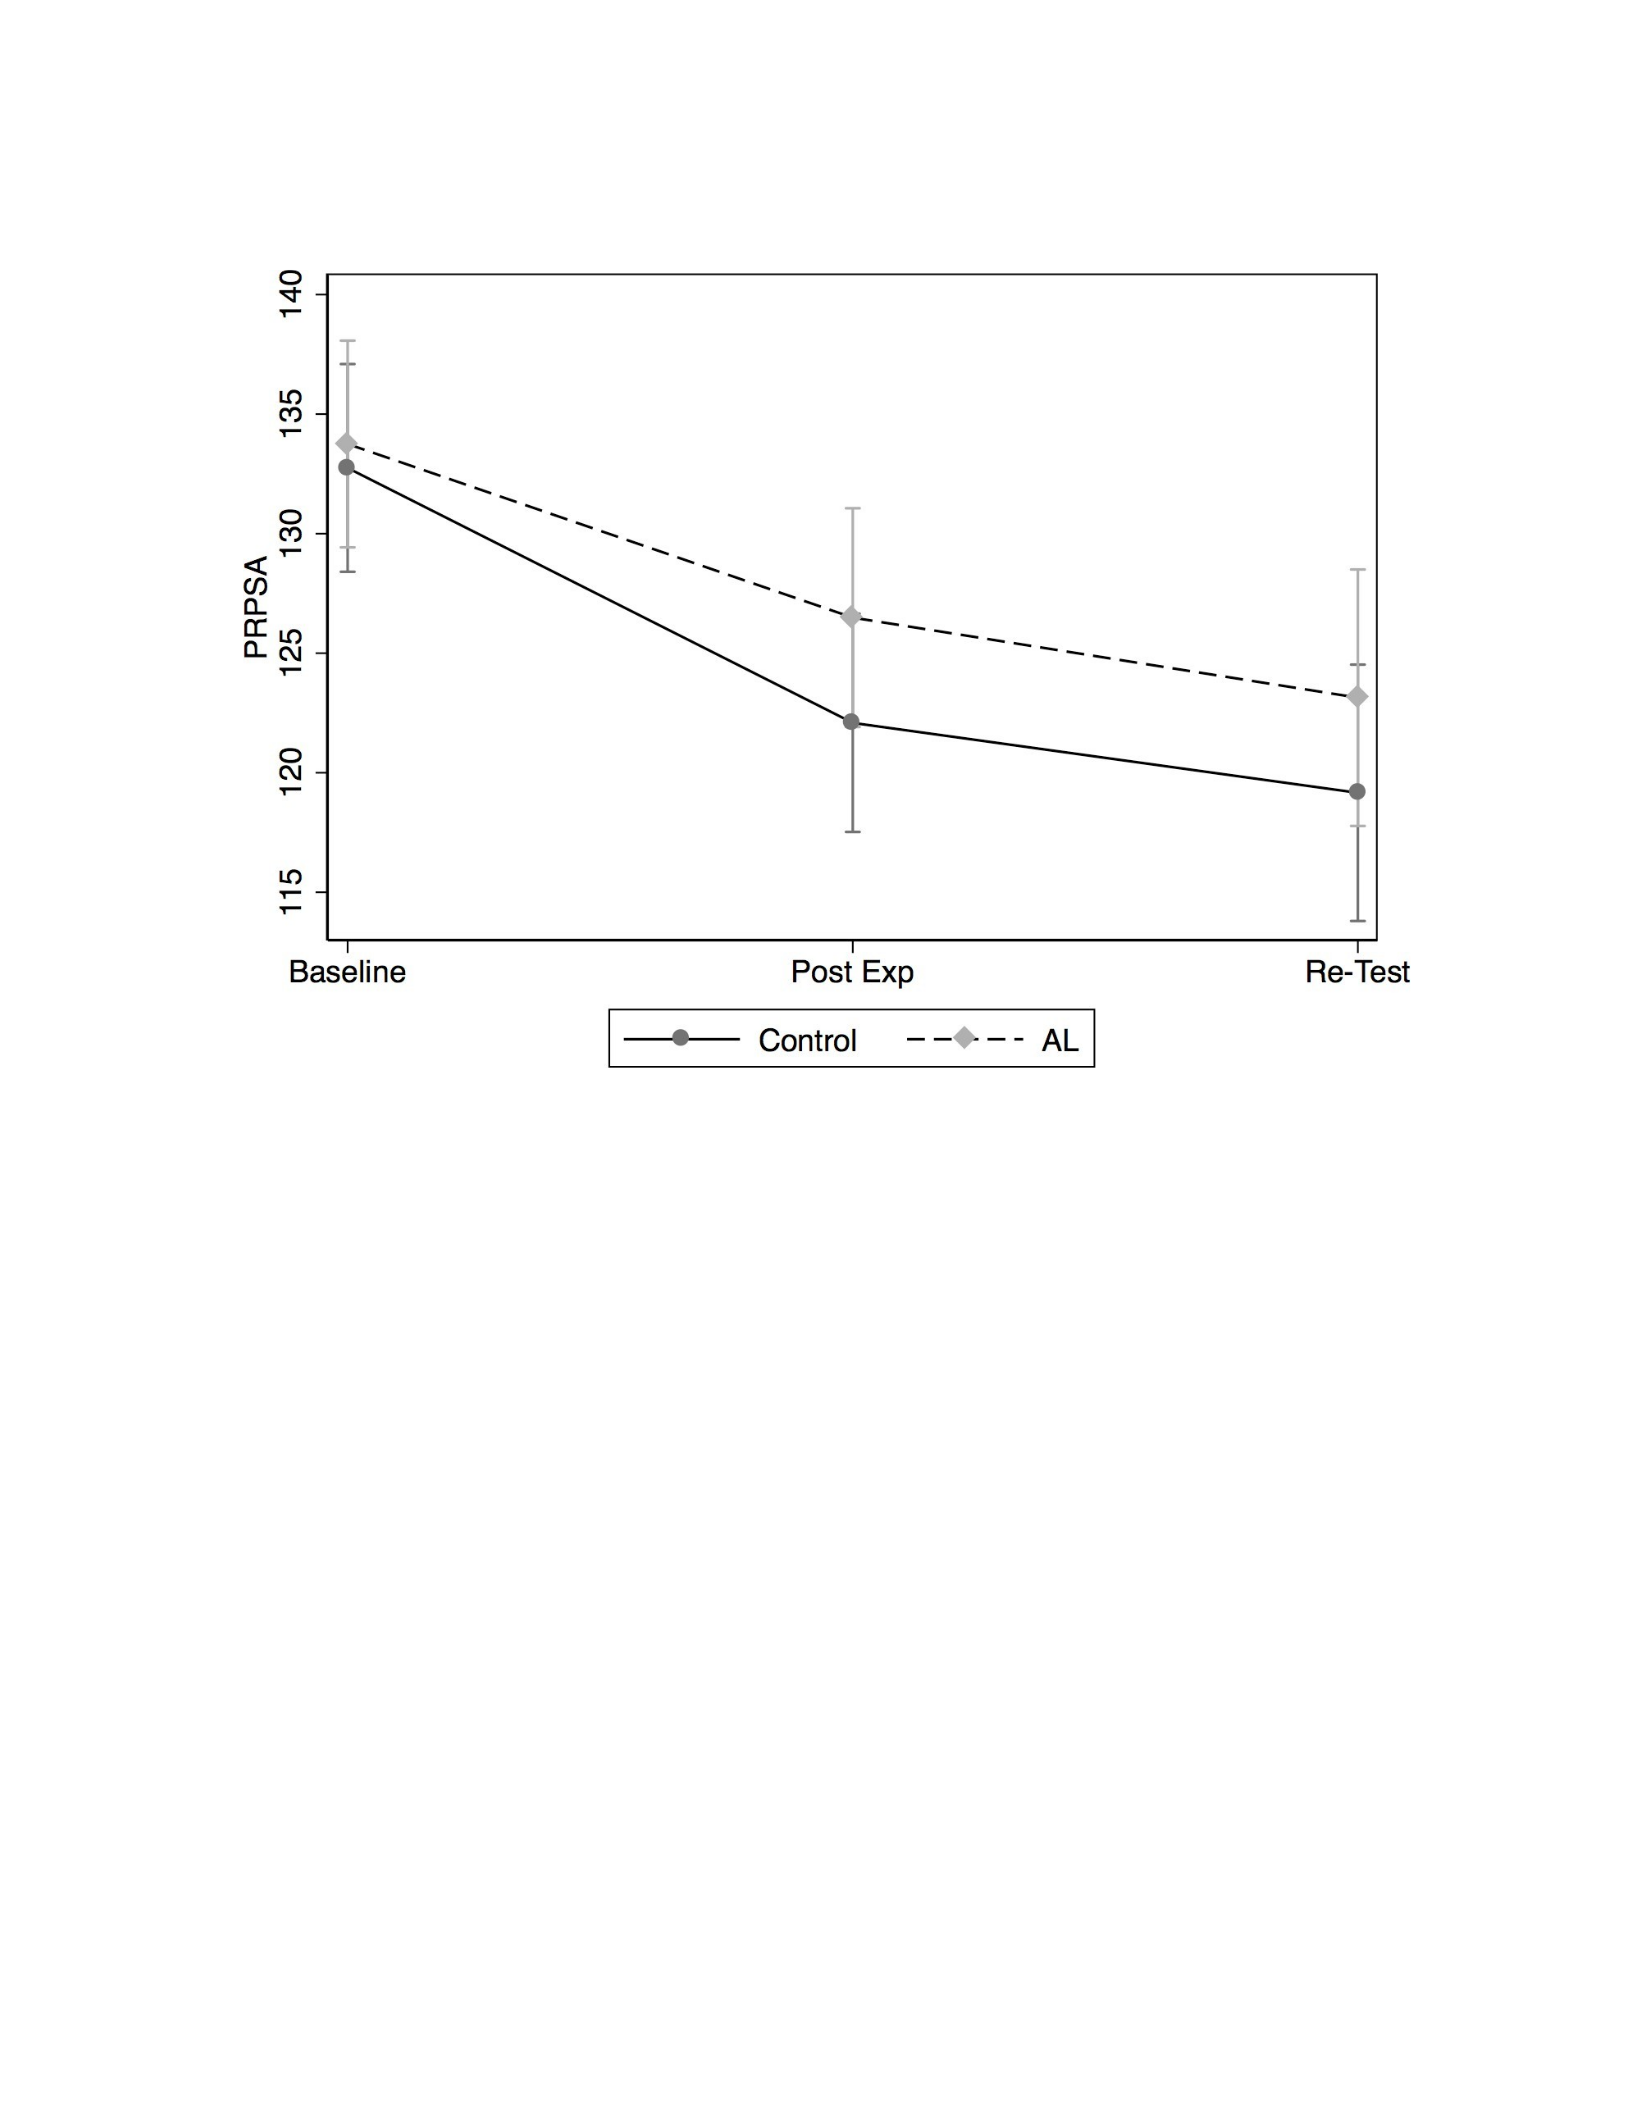
71
Figure 9. Personal Report of Public Speaking Anxiety Over Time by Group
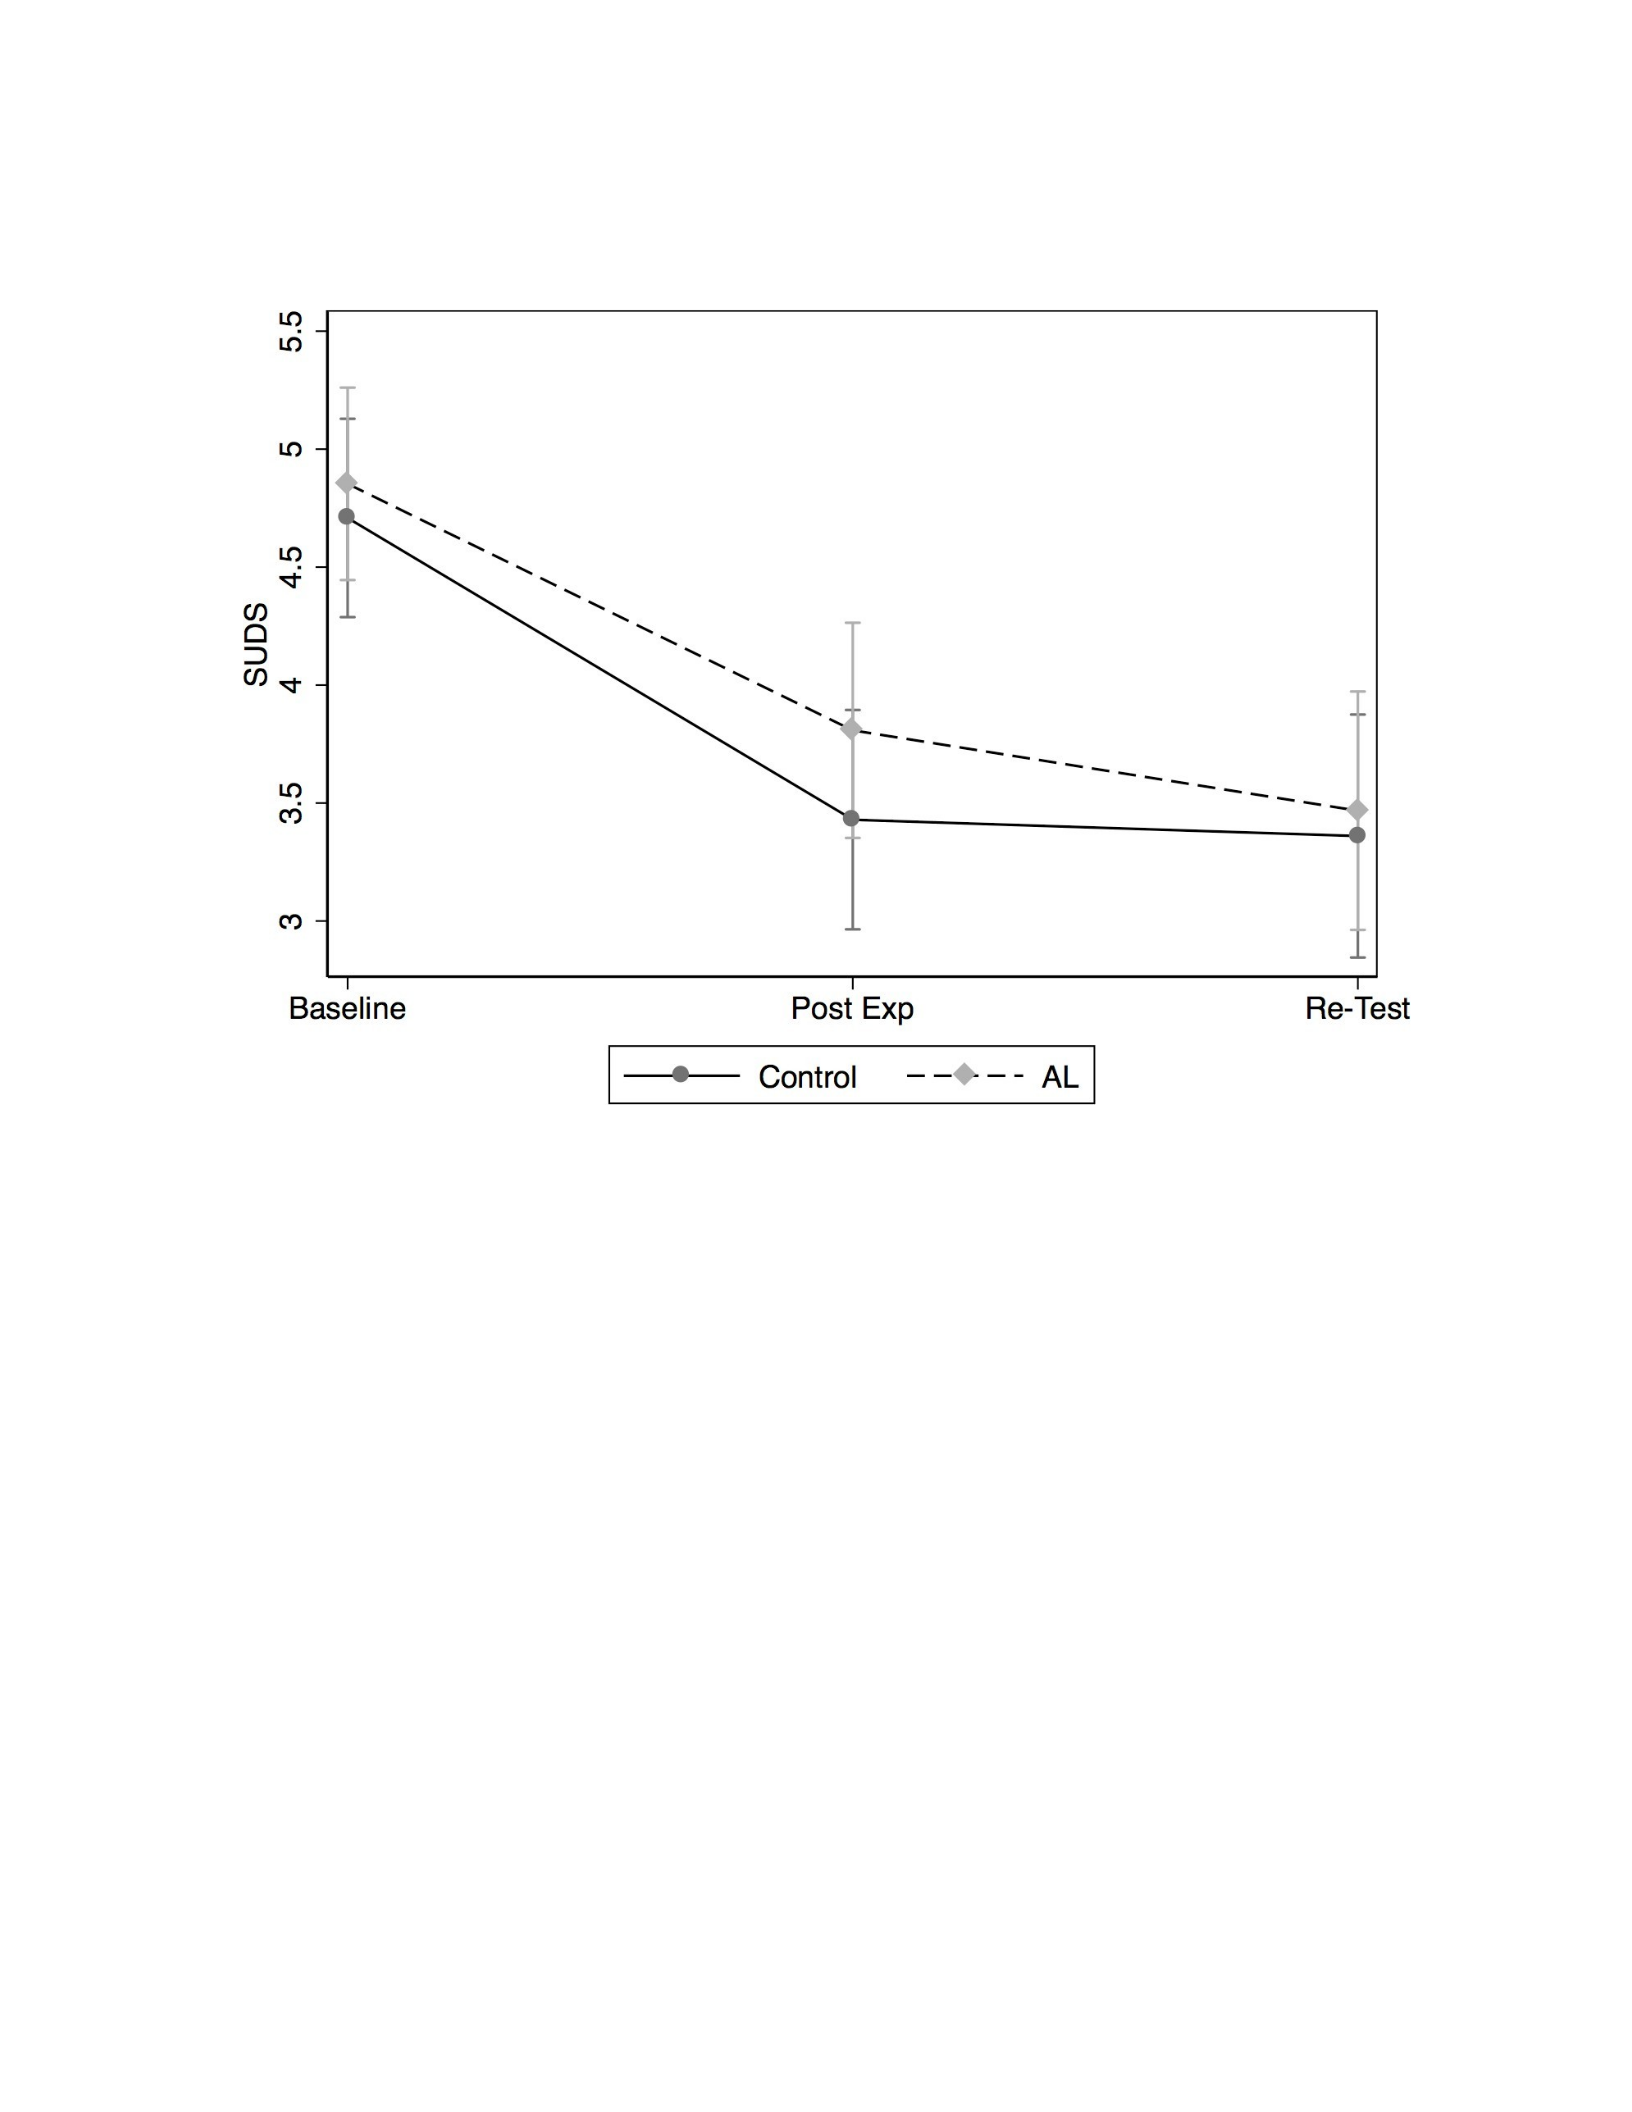
72
Figure 10. Subjective Units of Distress Over Time by Group
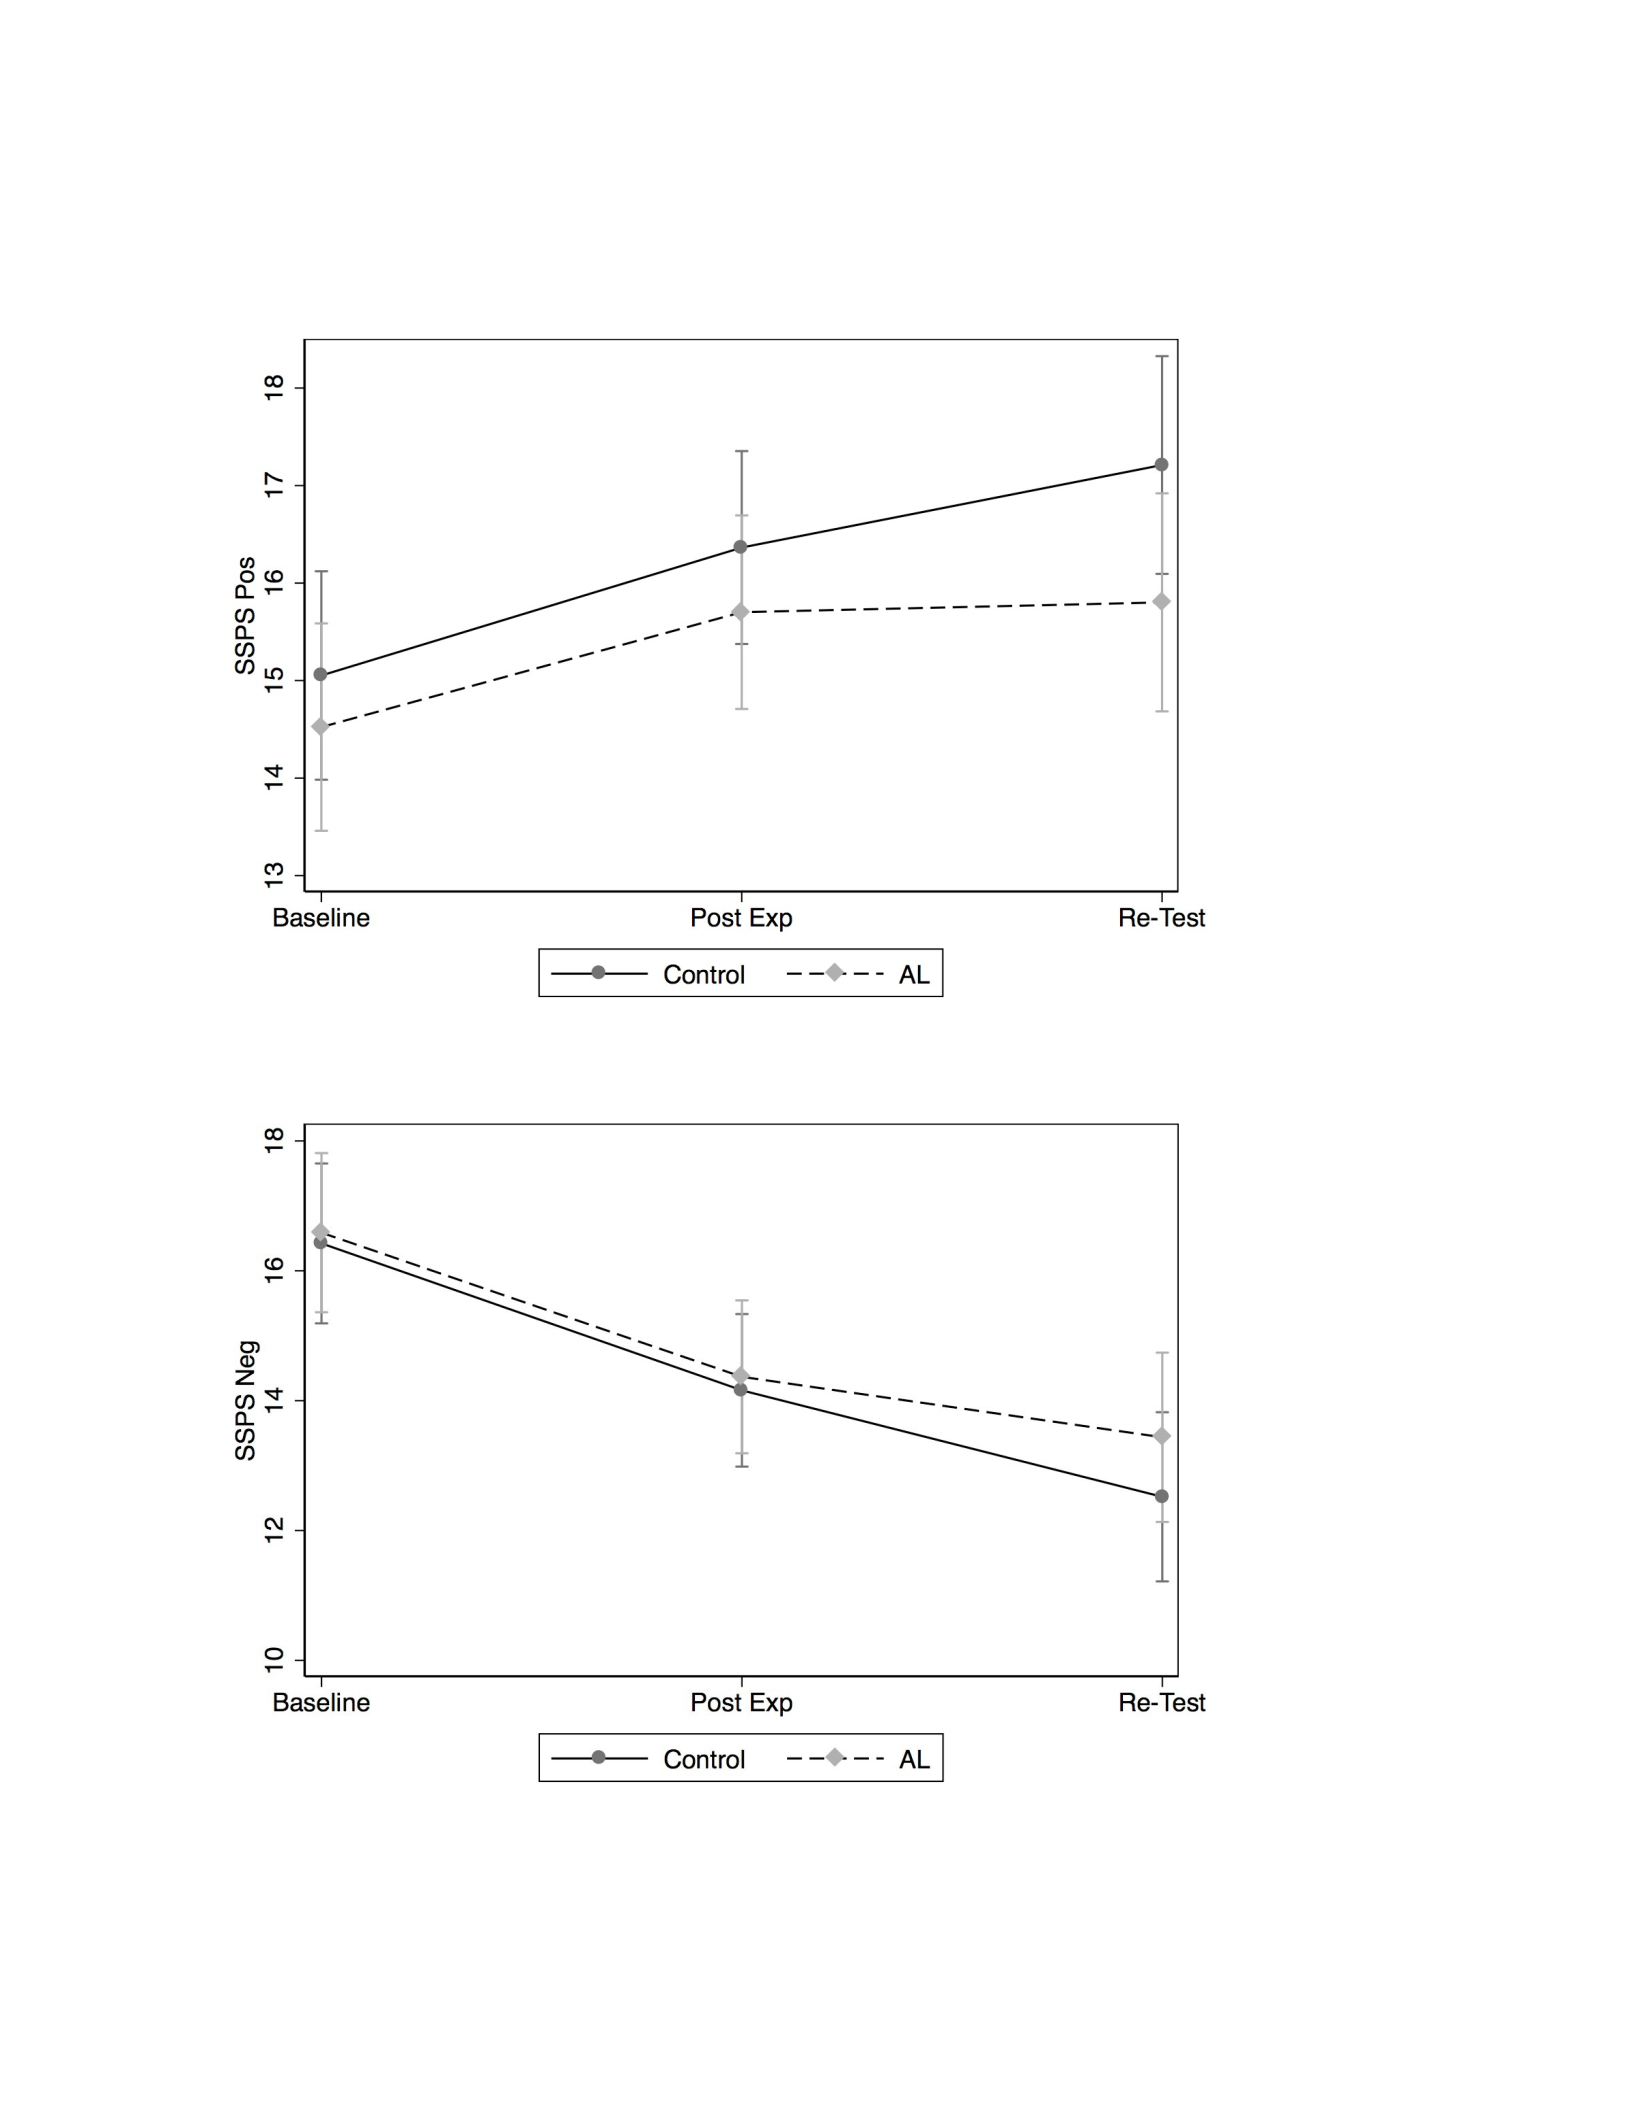
73
Figure 11. Self Statements During Public Speaking Over Time by Group: (A) Positive Self
Statements; (B) Negative Self Statements
(A)
(B)
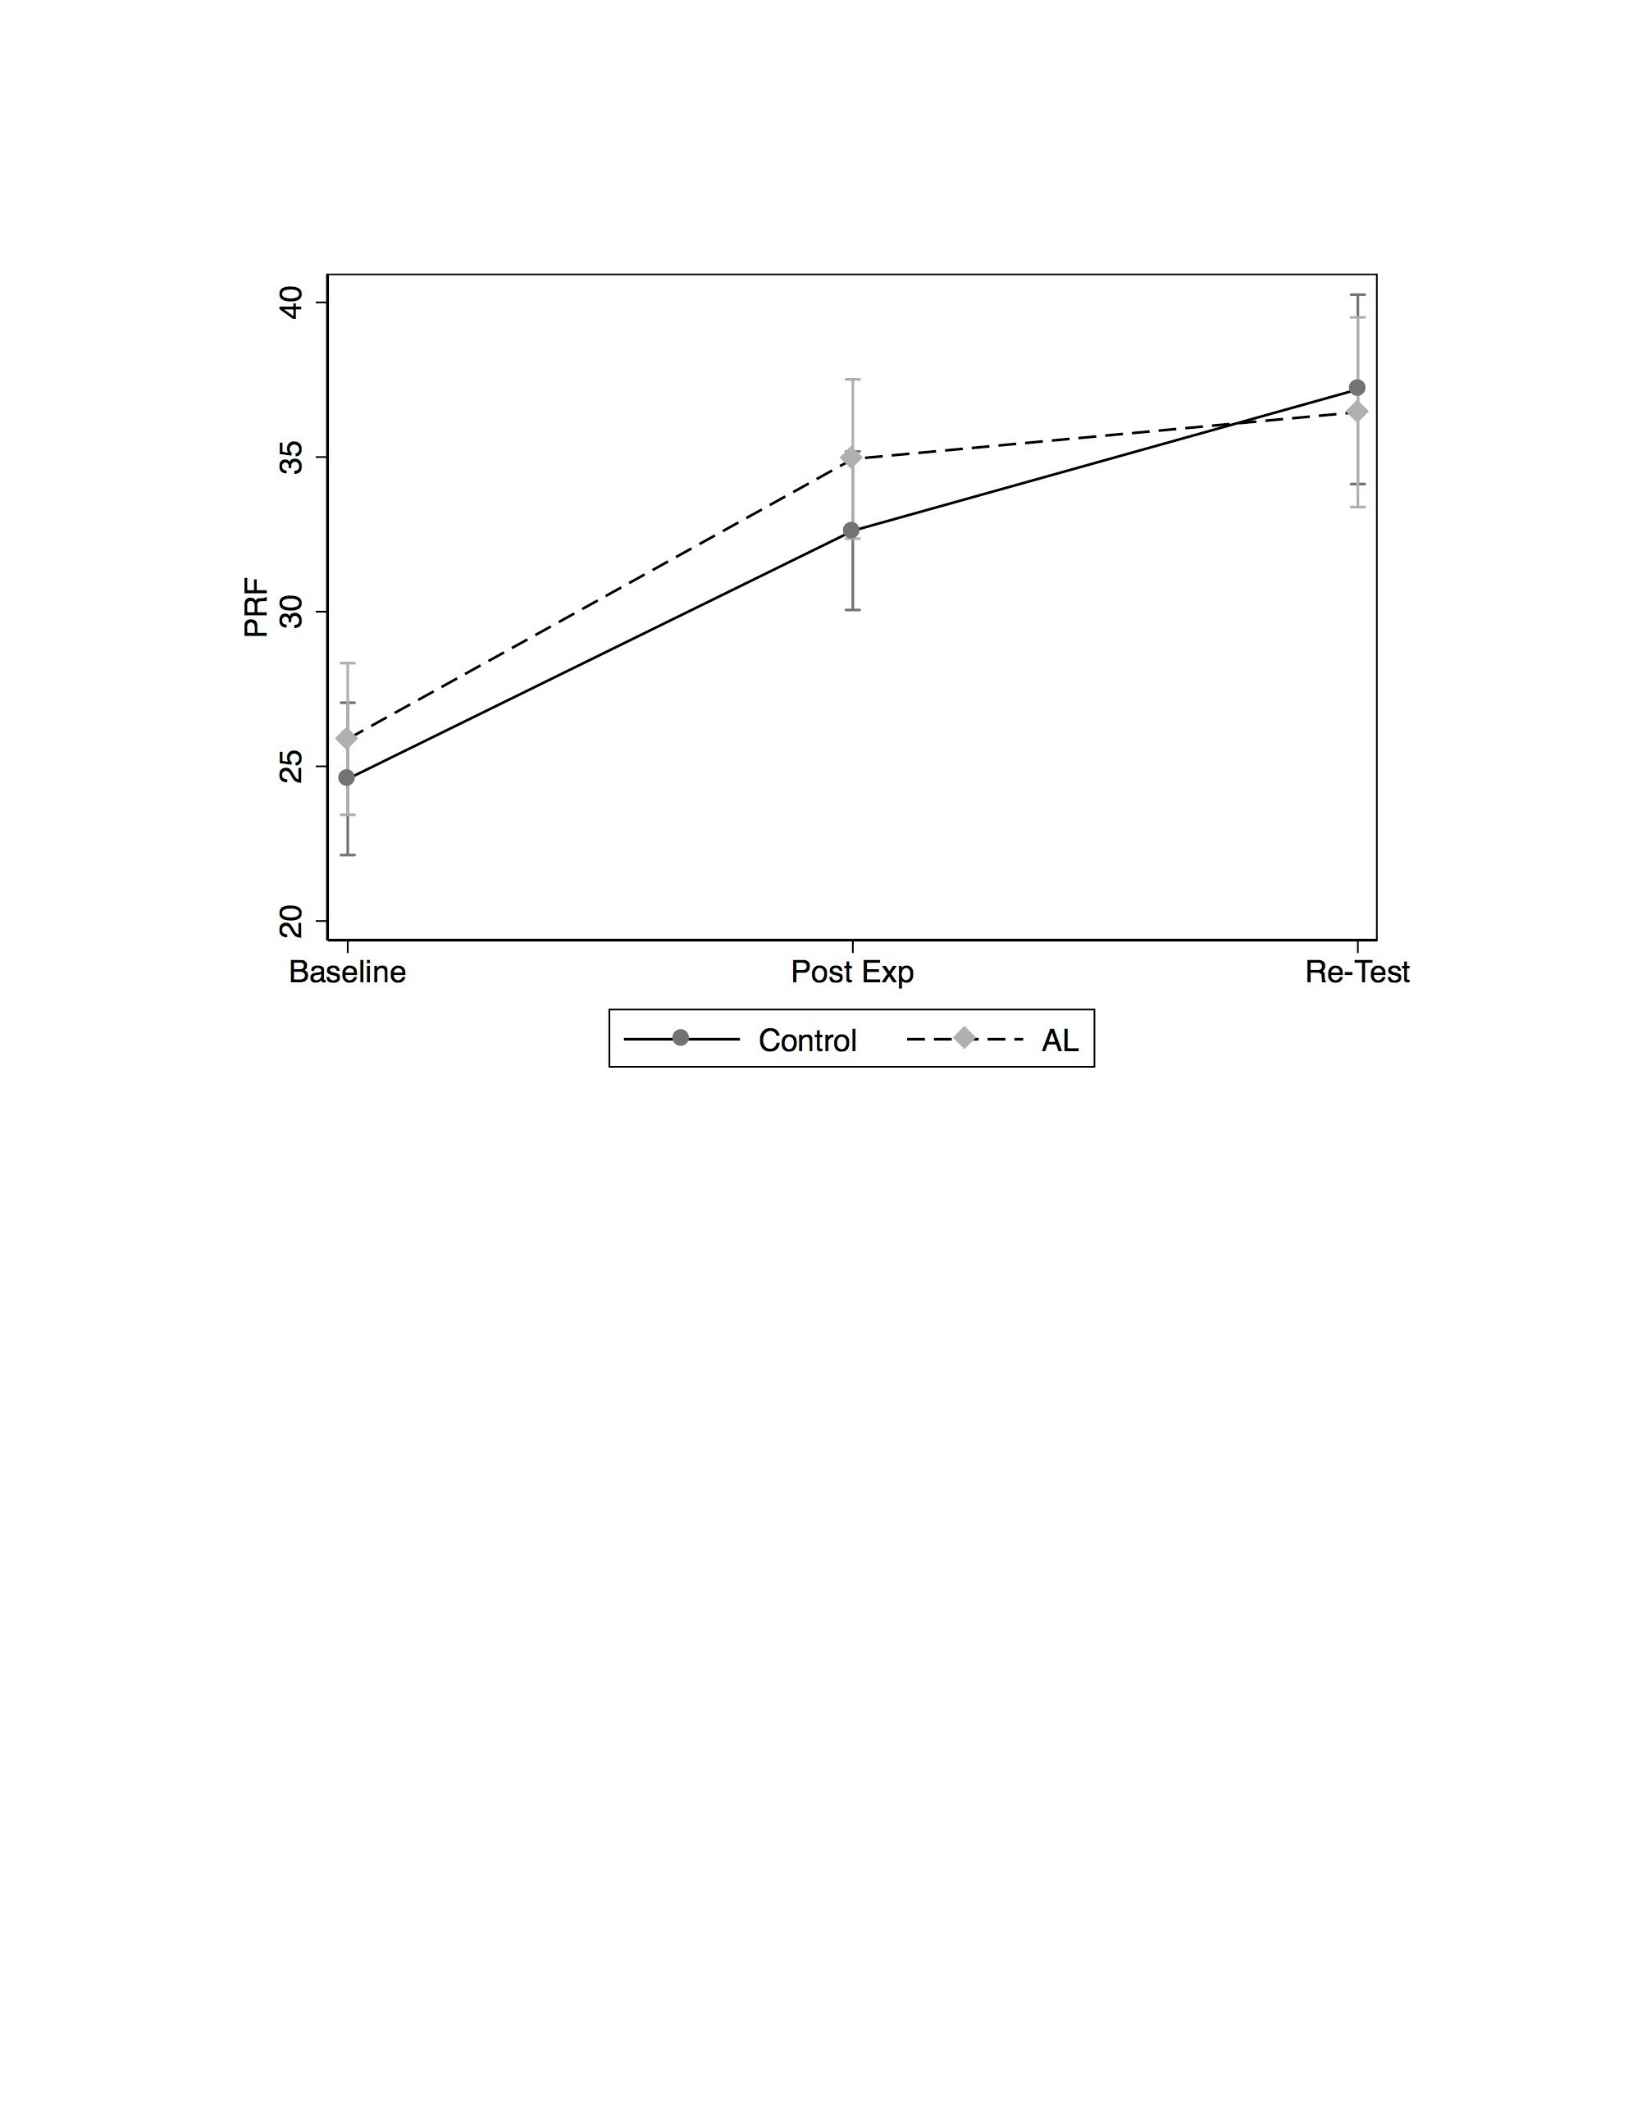
74
Figure 12. Performance Rating Form Over Time by Group
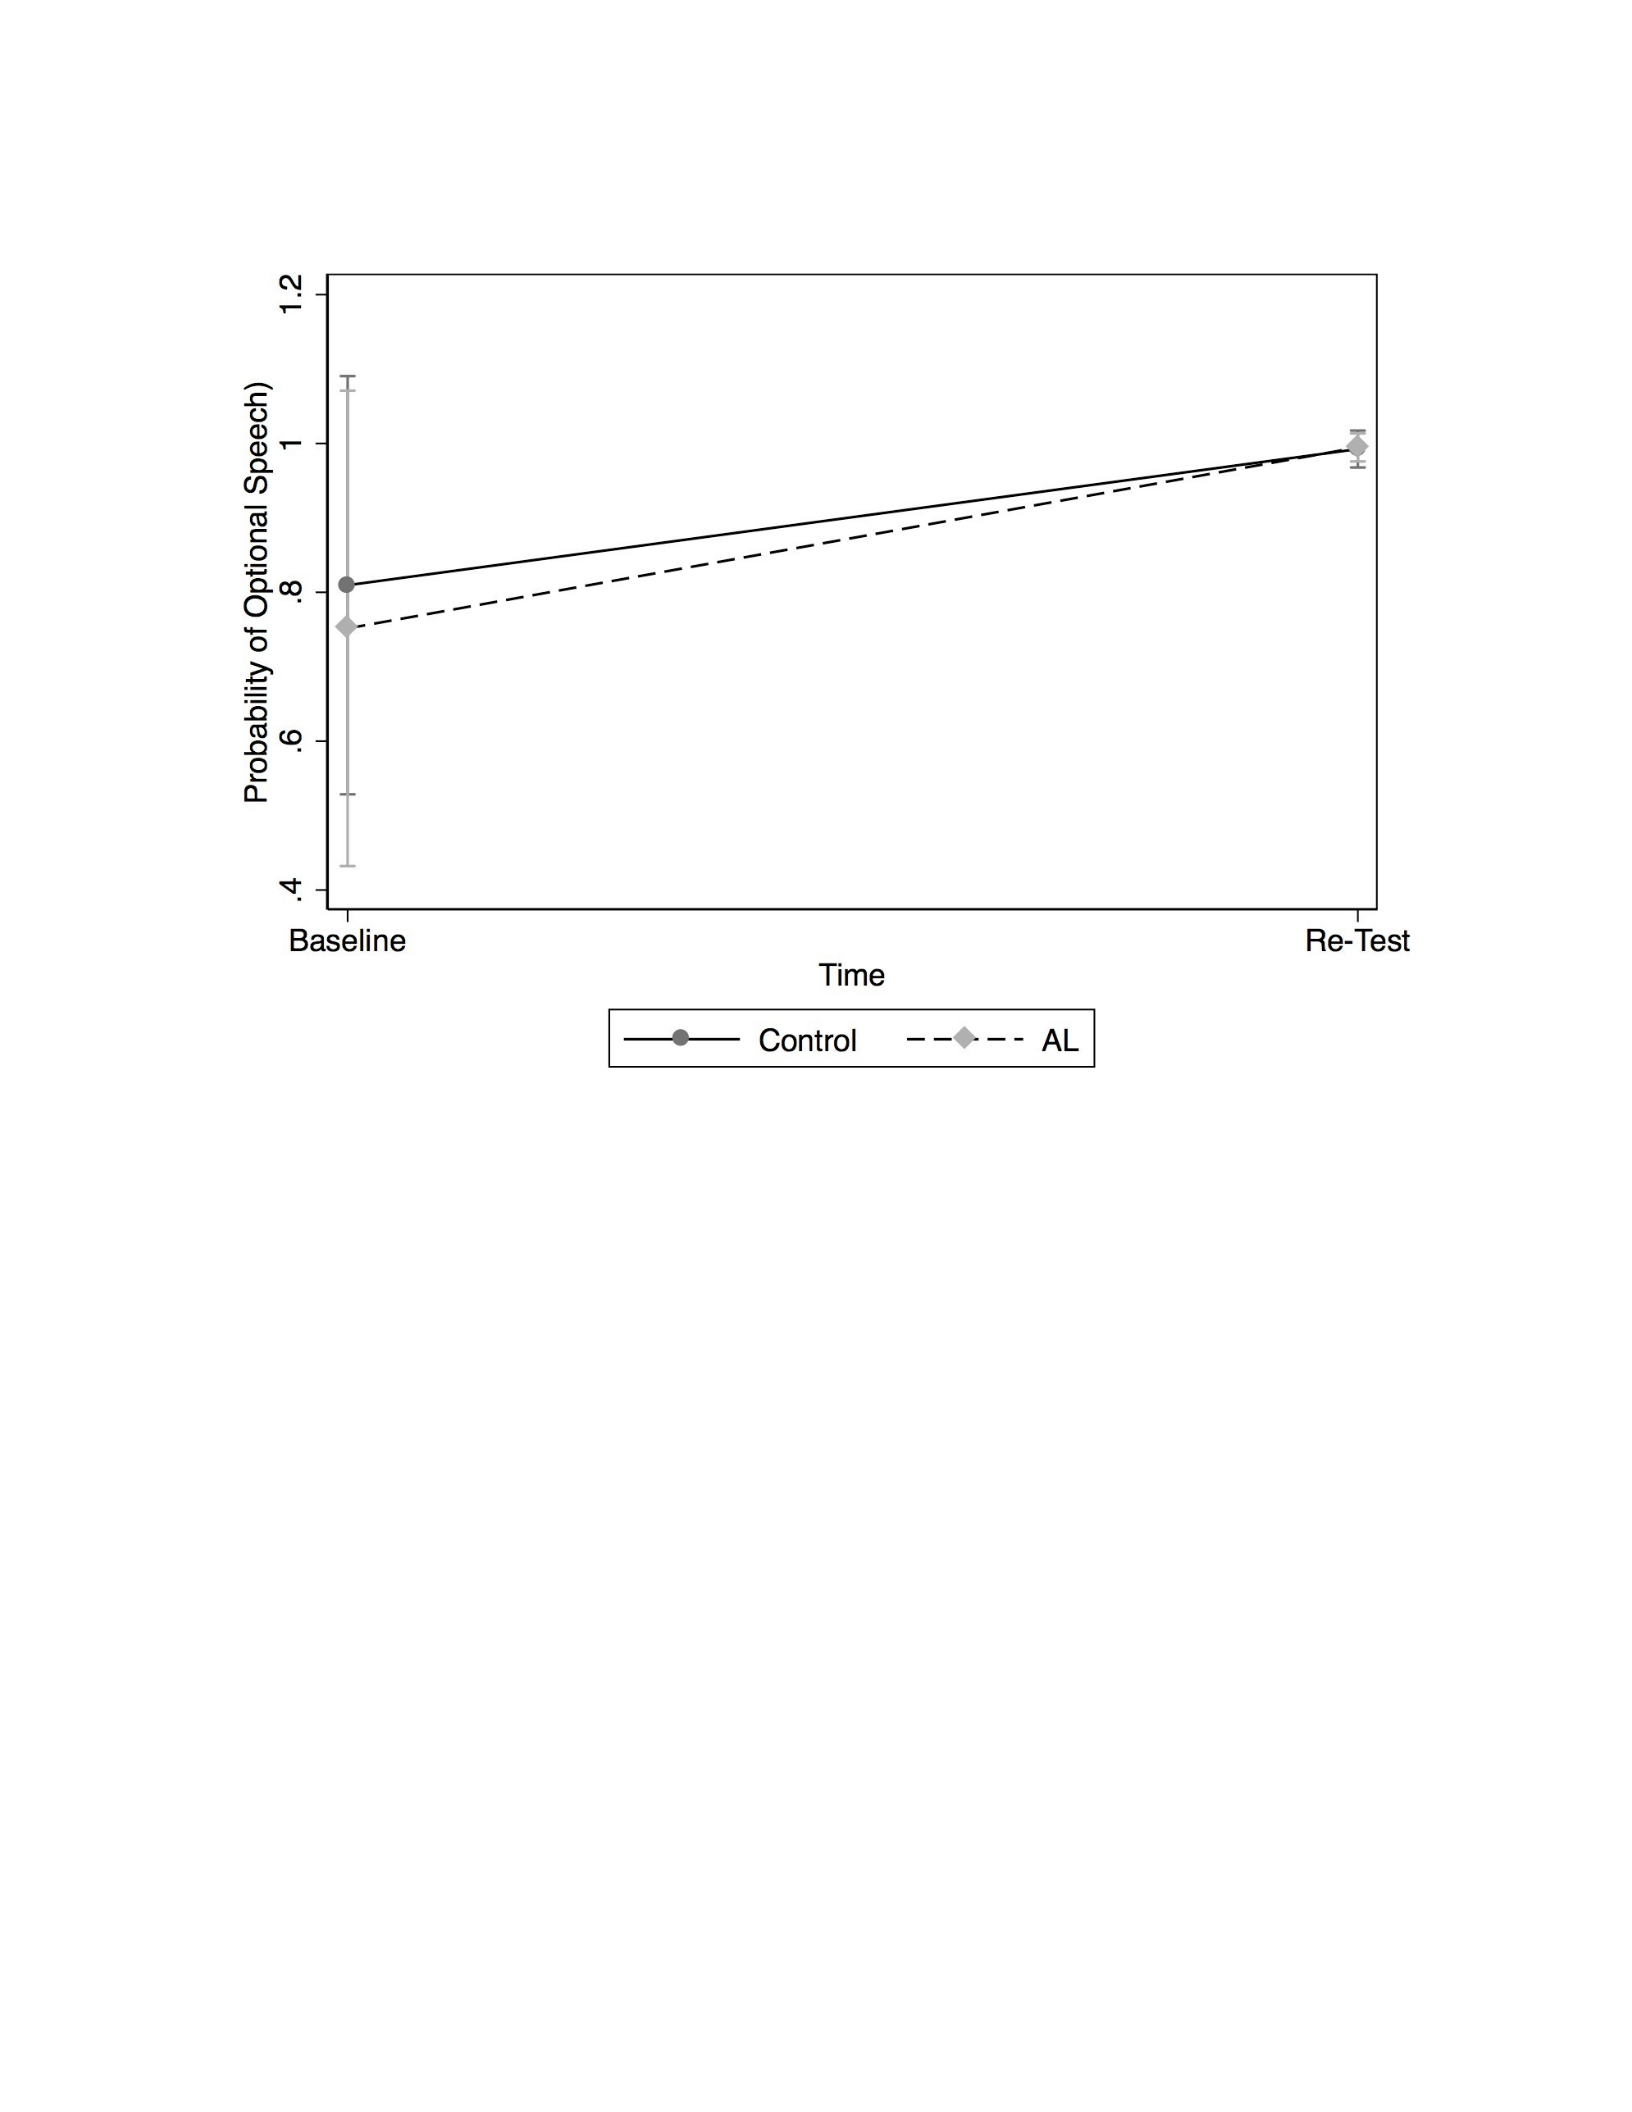
75
Figure 13. Optional Speech Over Time by Group
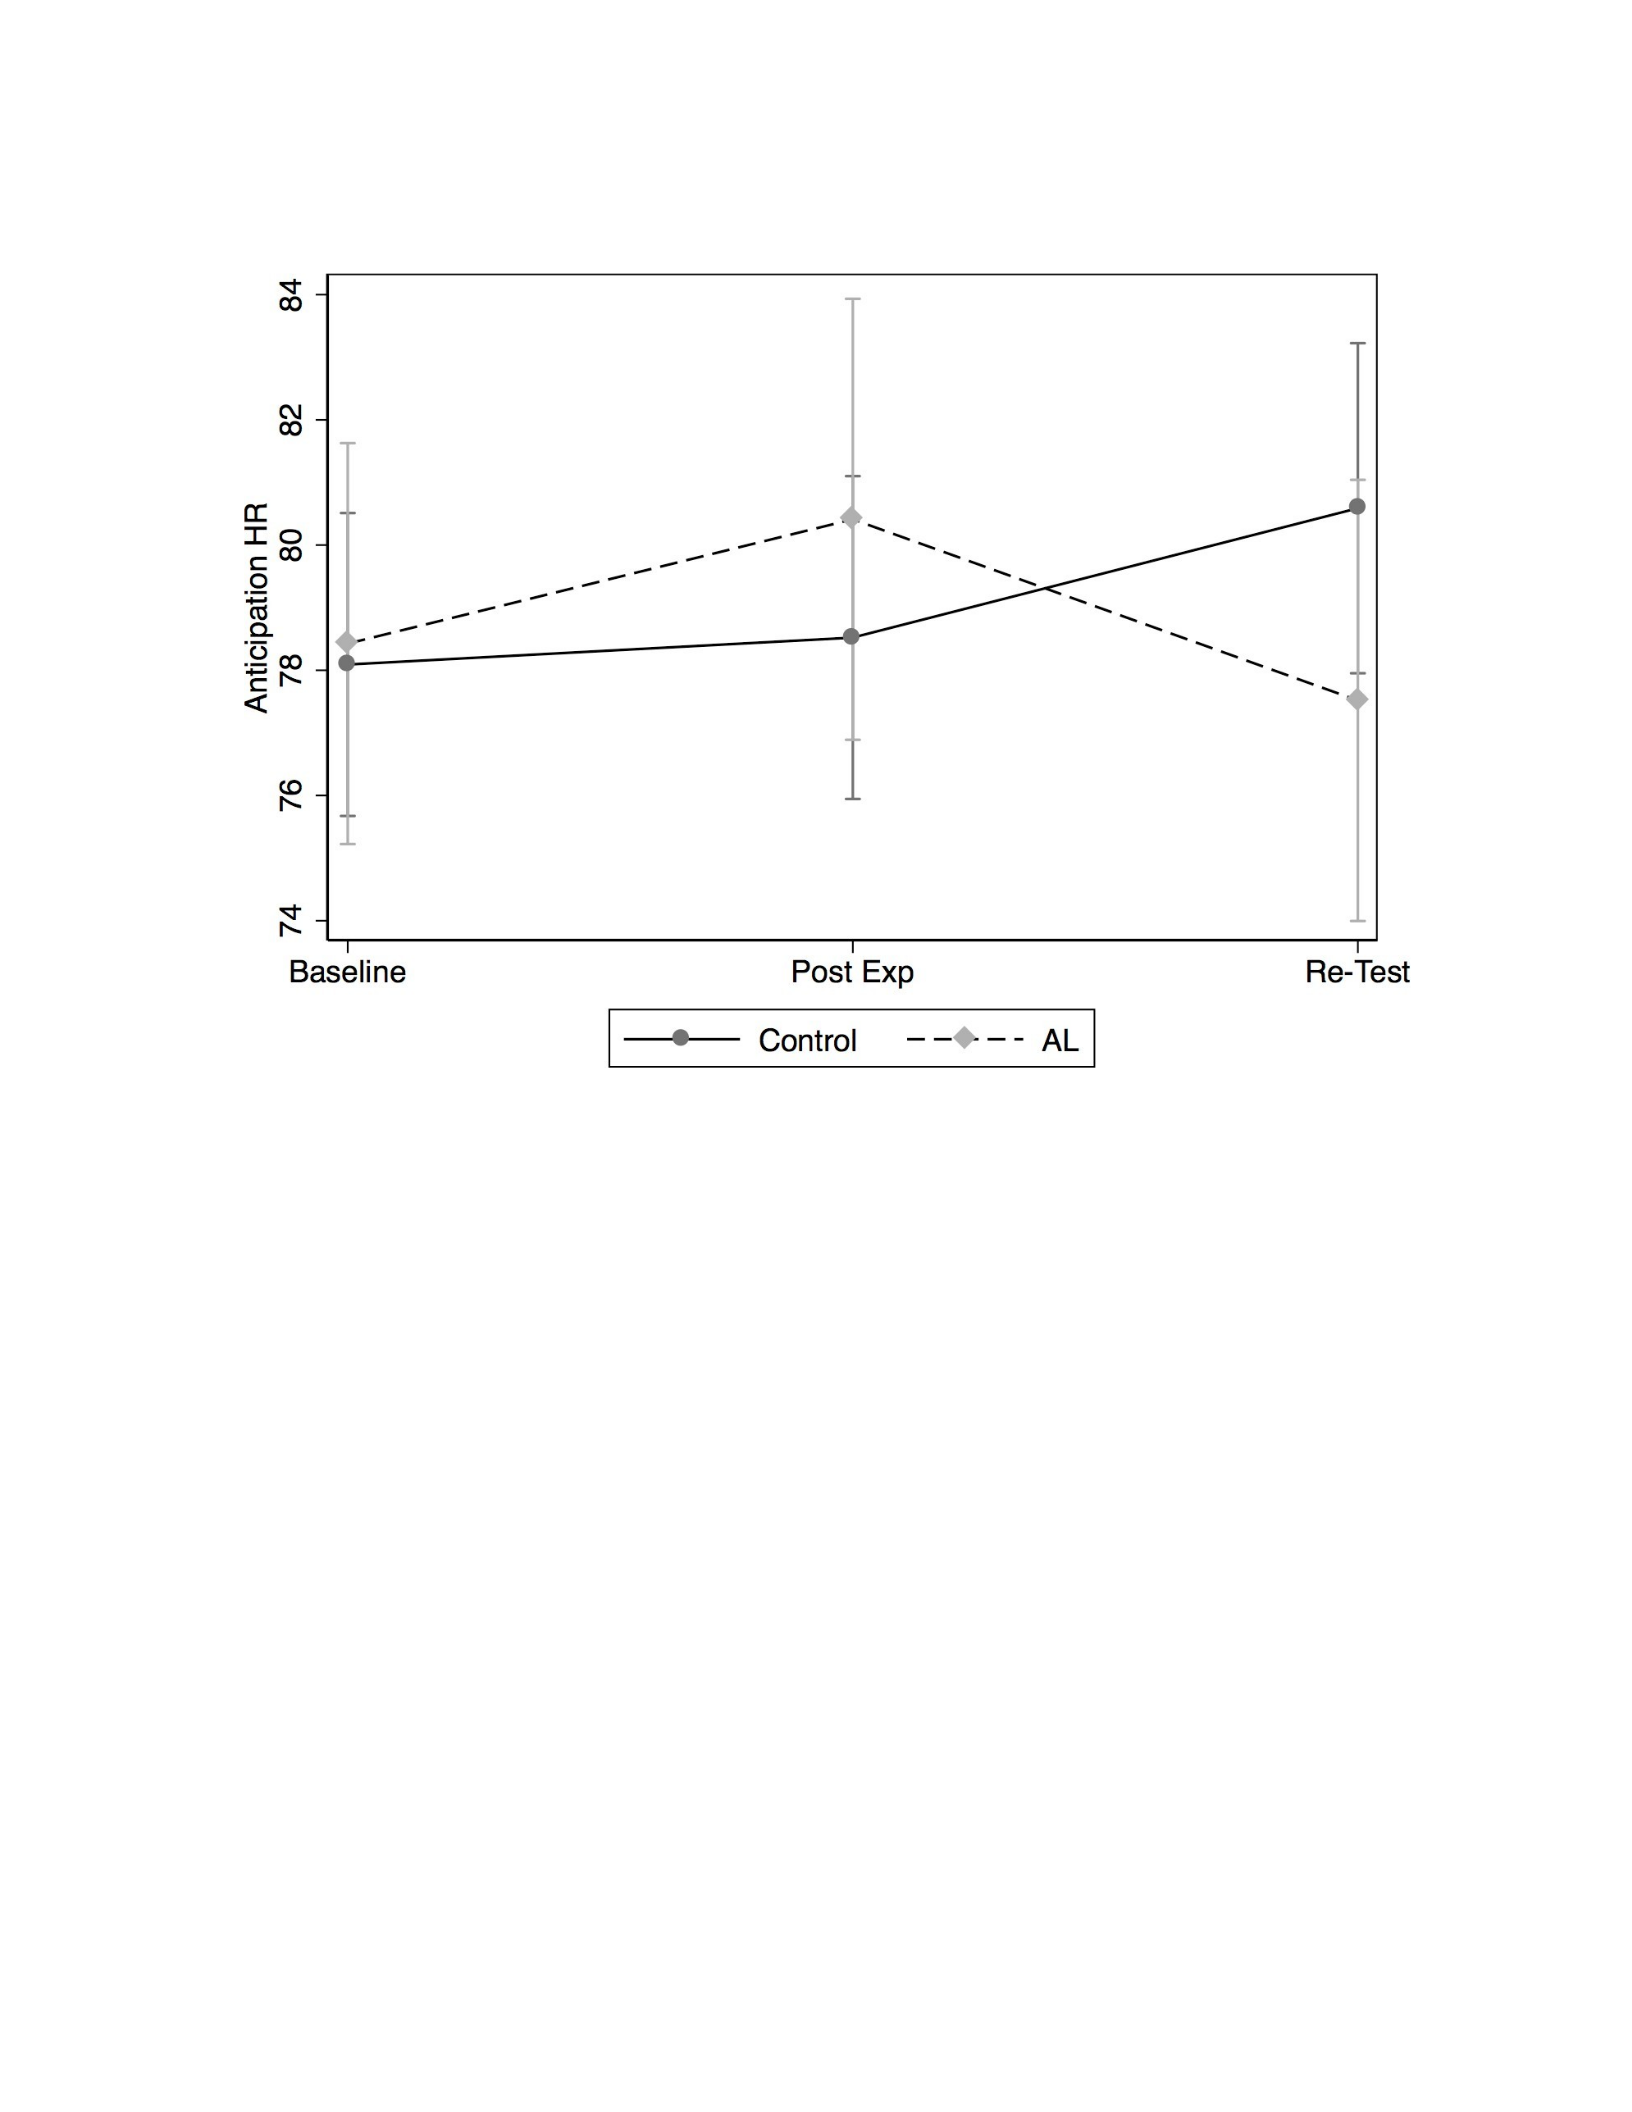
76
Figure 14. Heart Rate During Anticipation over Time by Group for High Labelers Only
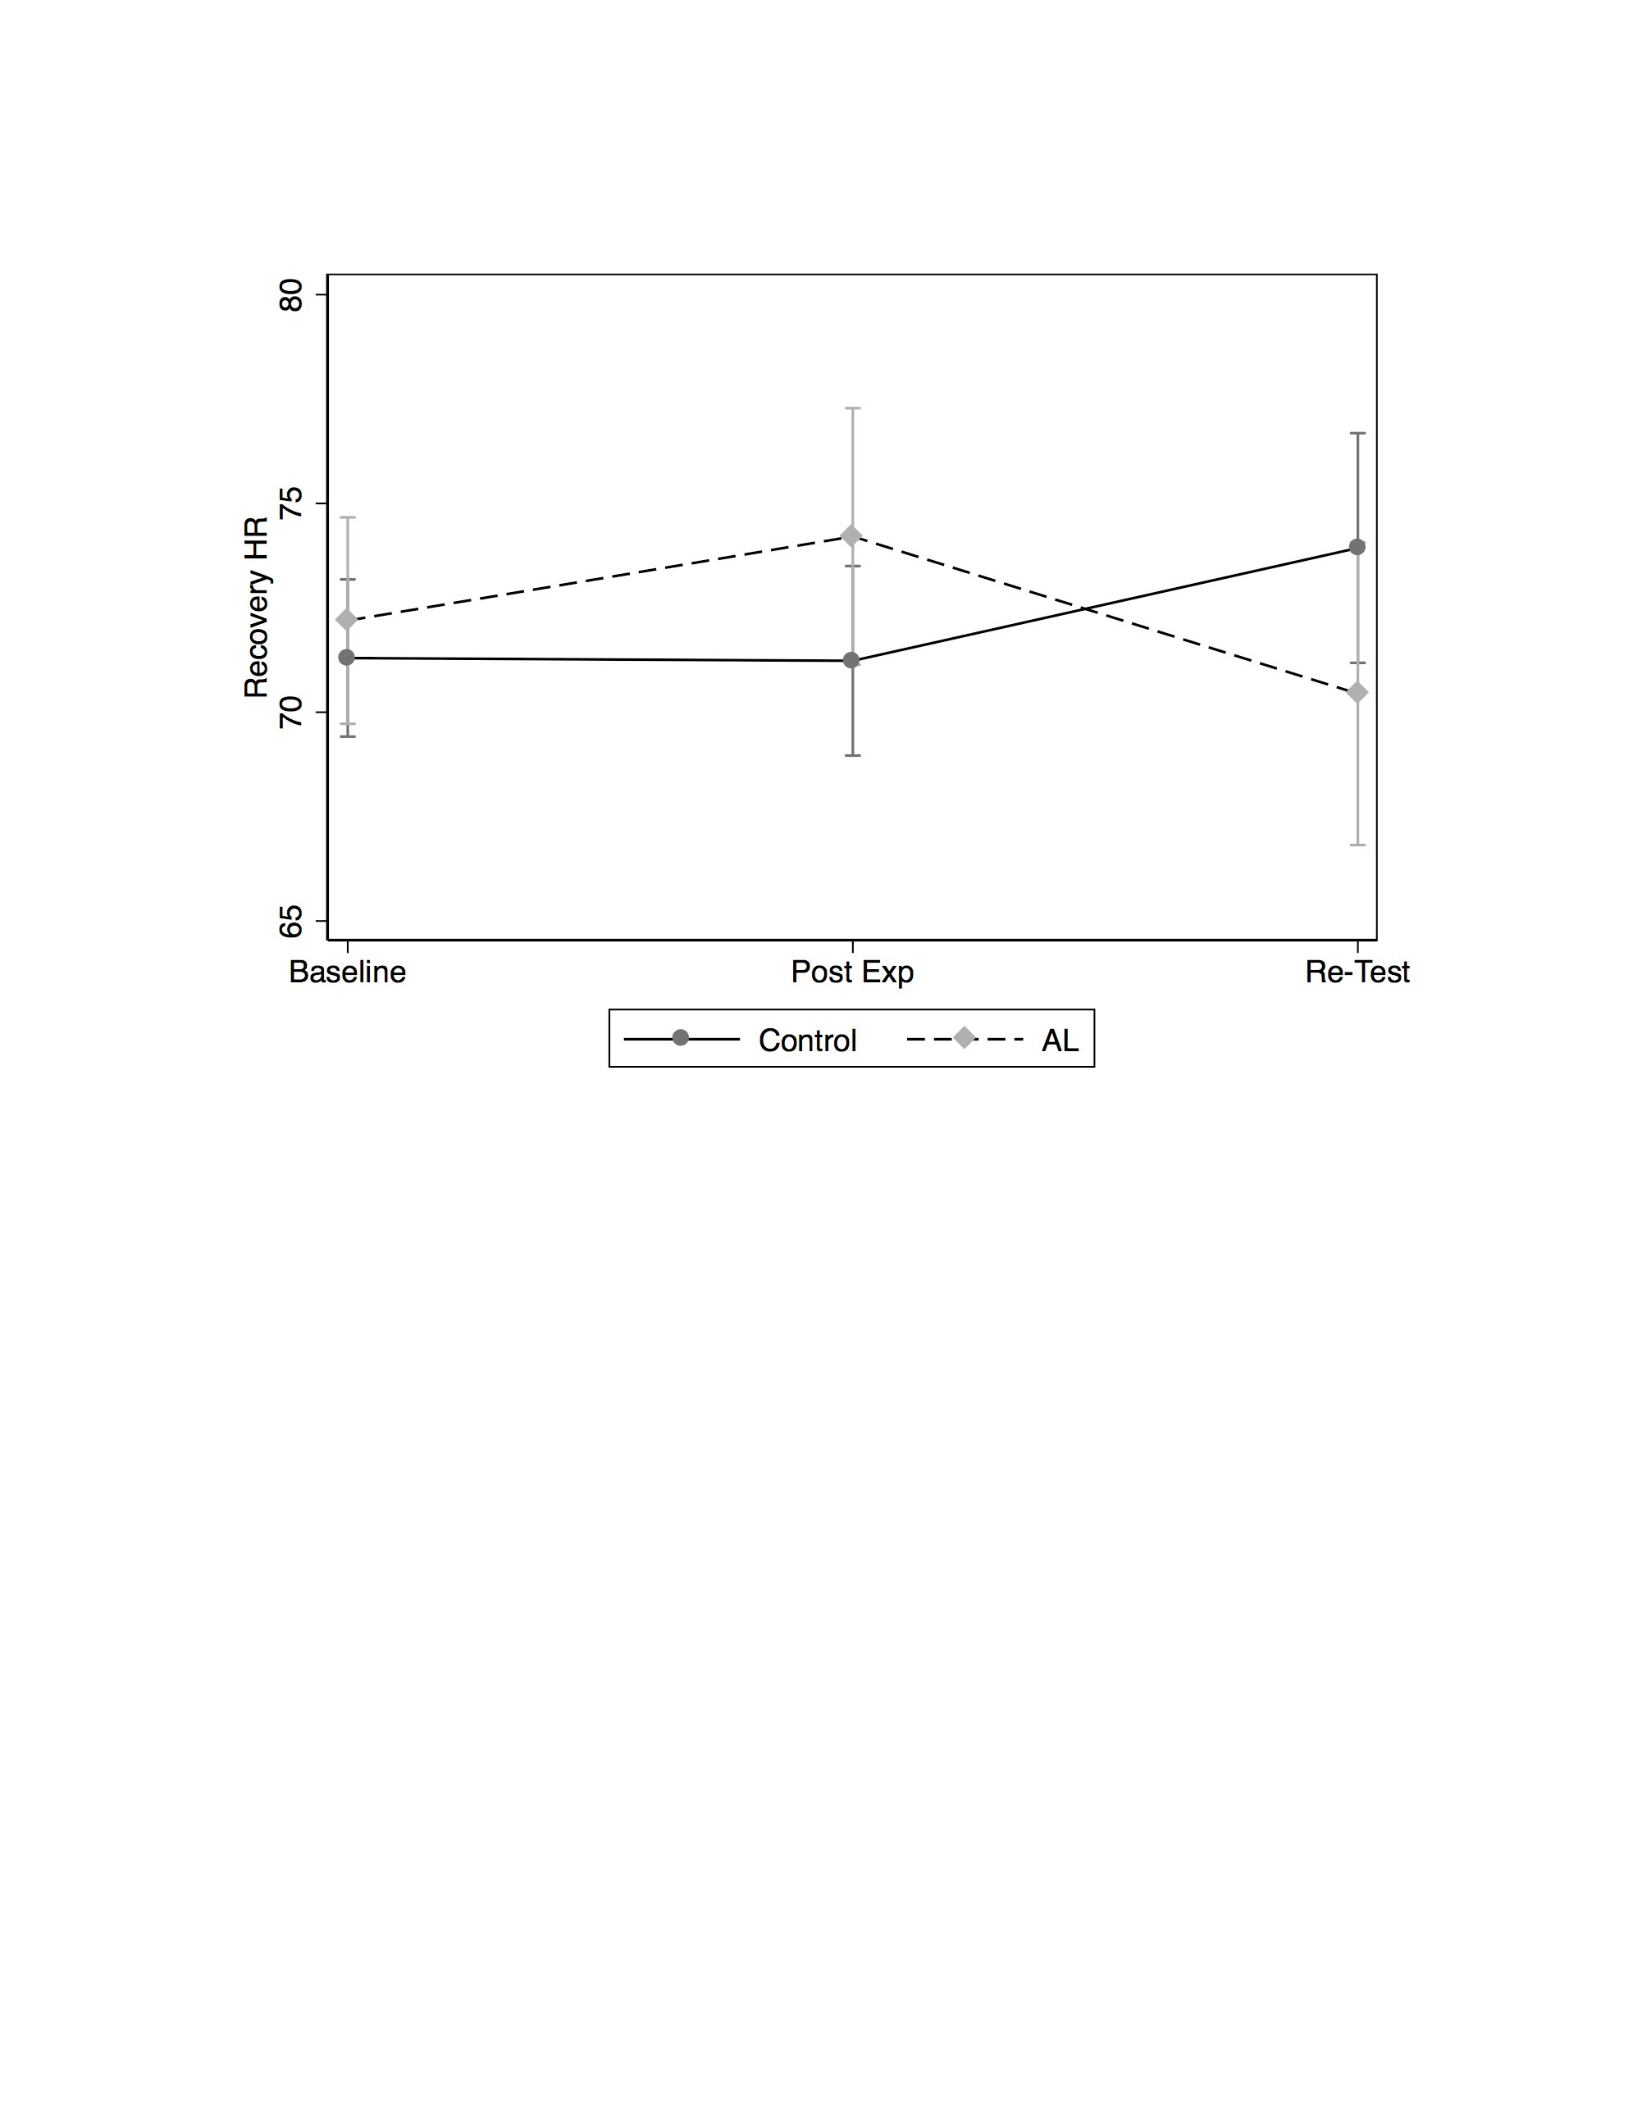
77
Figure 15. Heart Rate During Recovery over Time by Group for High Labelers Only
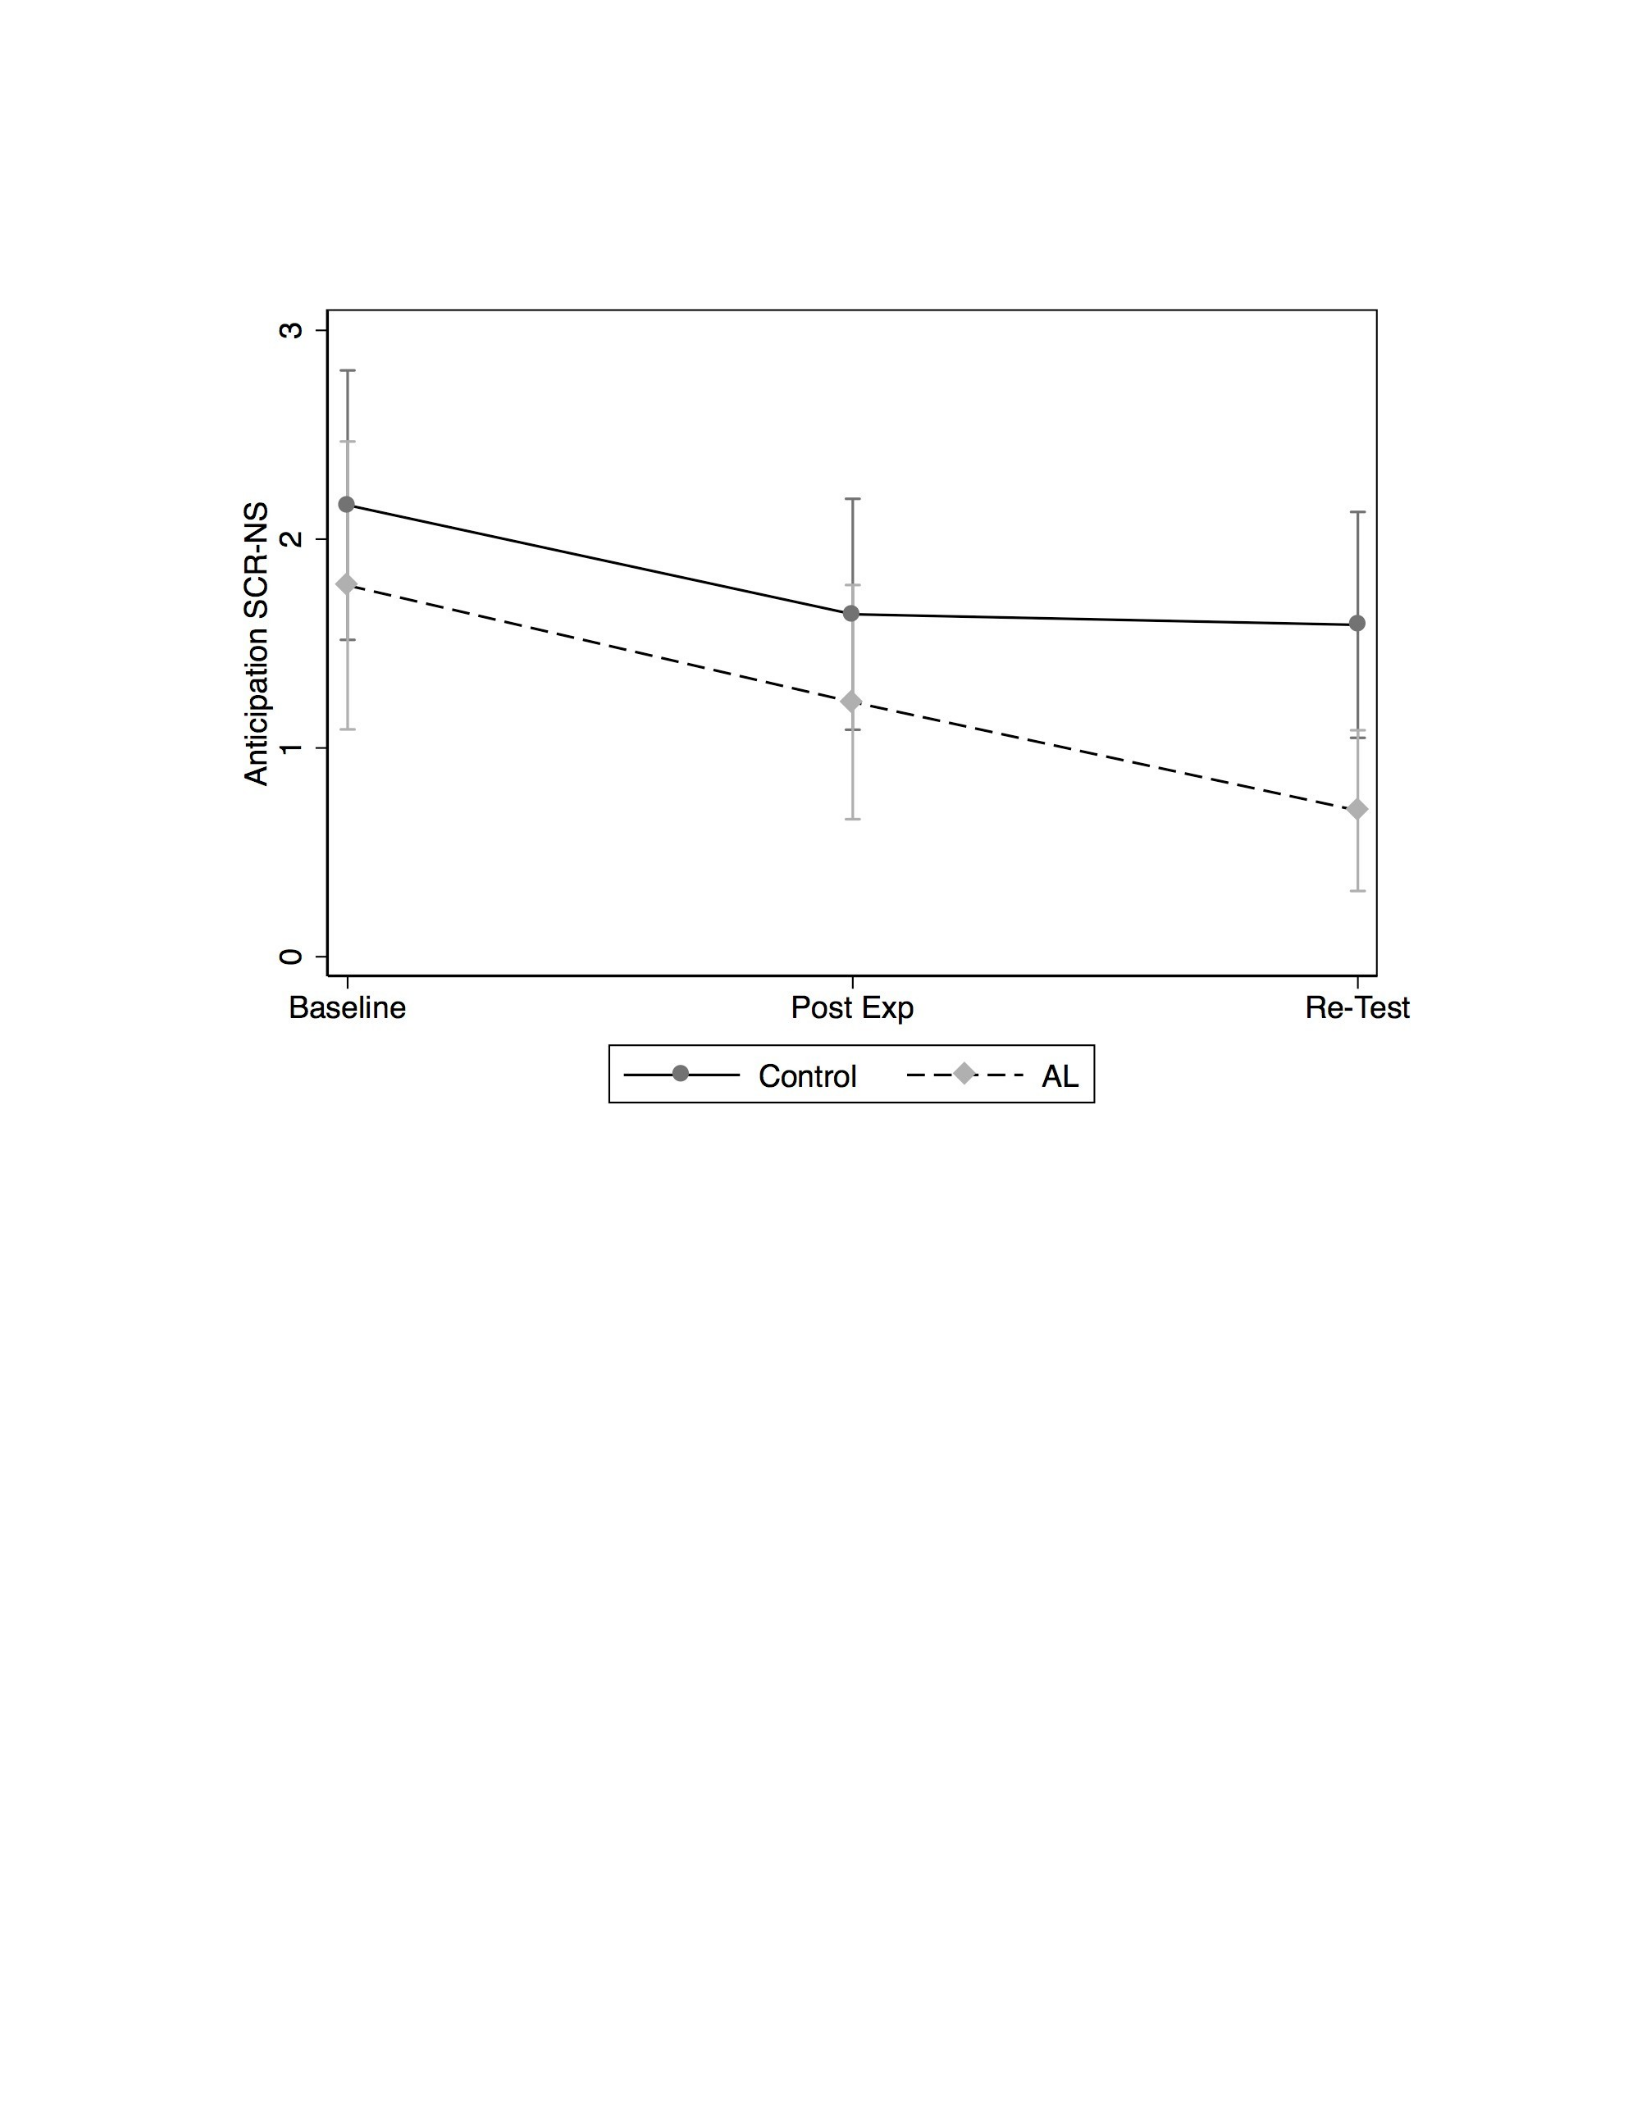
78
Figure 16. Non-Specific Skin Conductance Response during Anticipation over Time by Group
for High Labelers Only
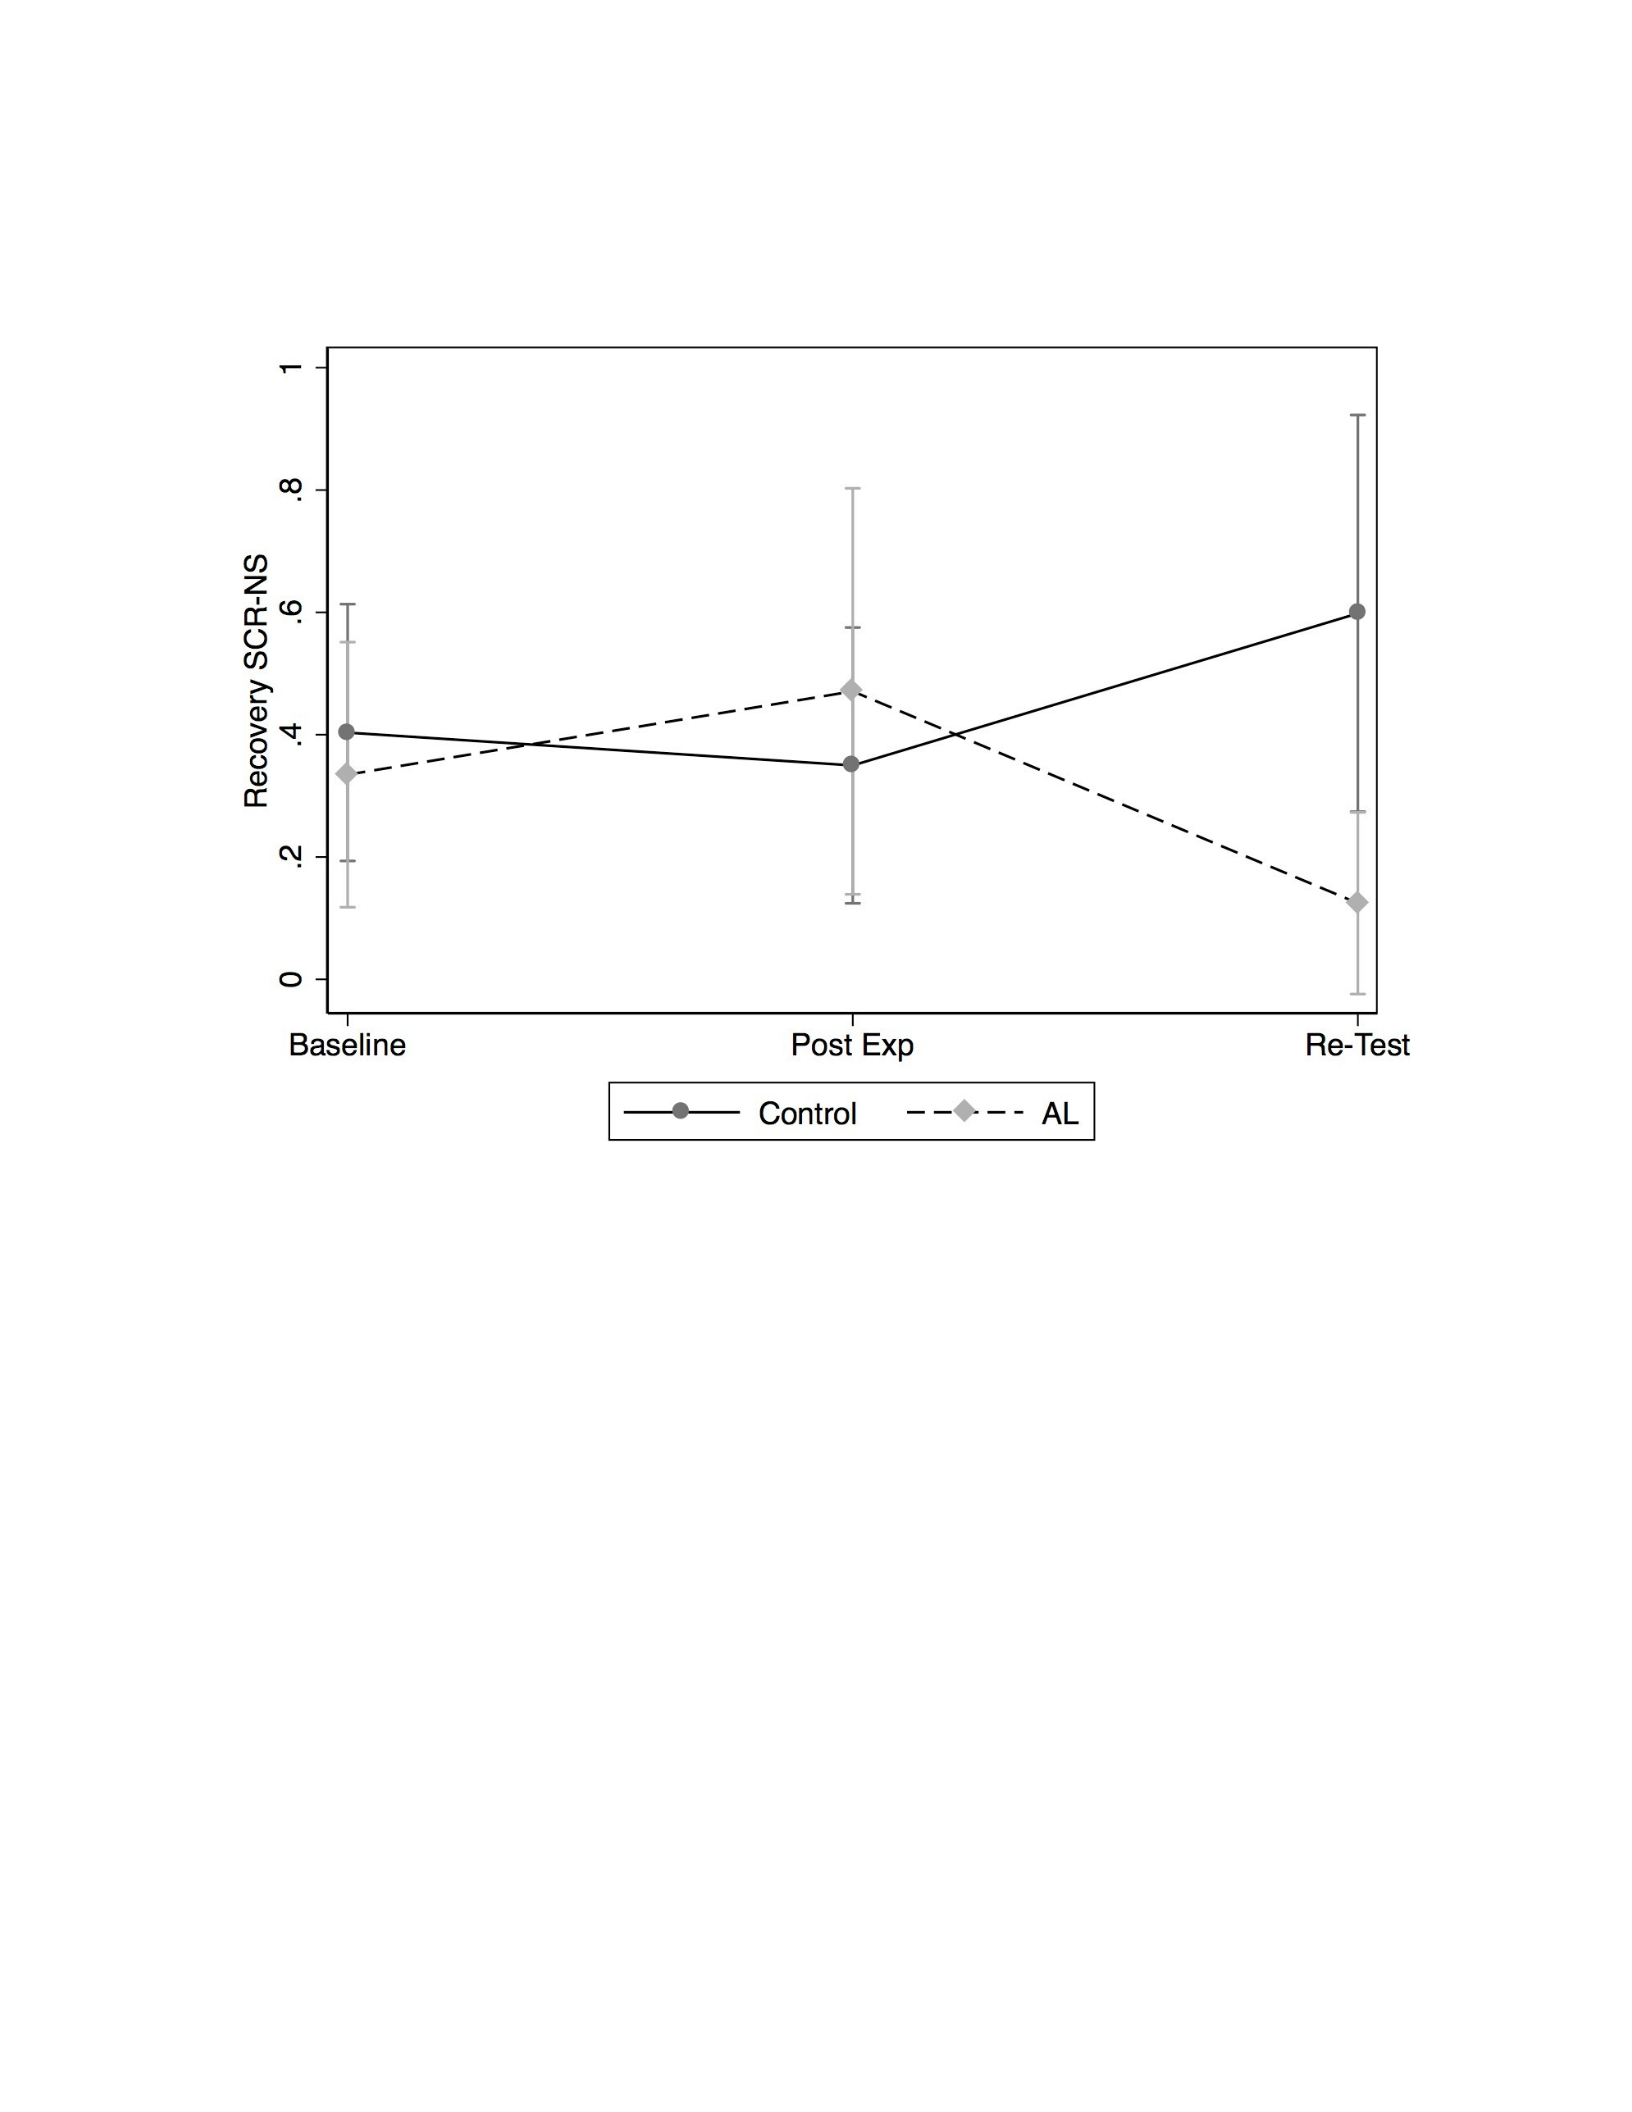
79
Figure 17. Non-Specific Skin Conductance Response During Recovery over Time by Group for
High Labelers Only
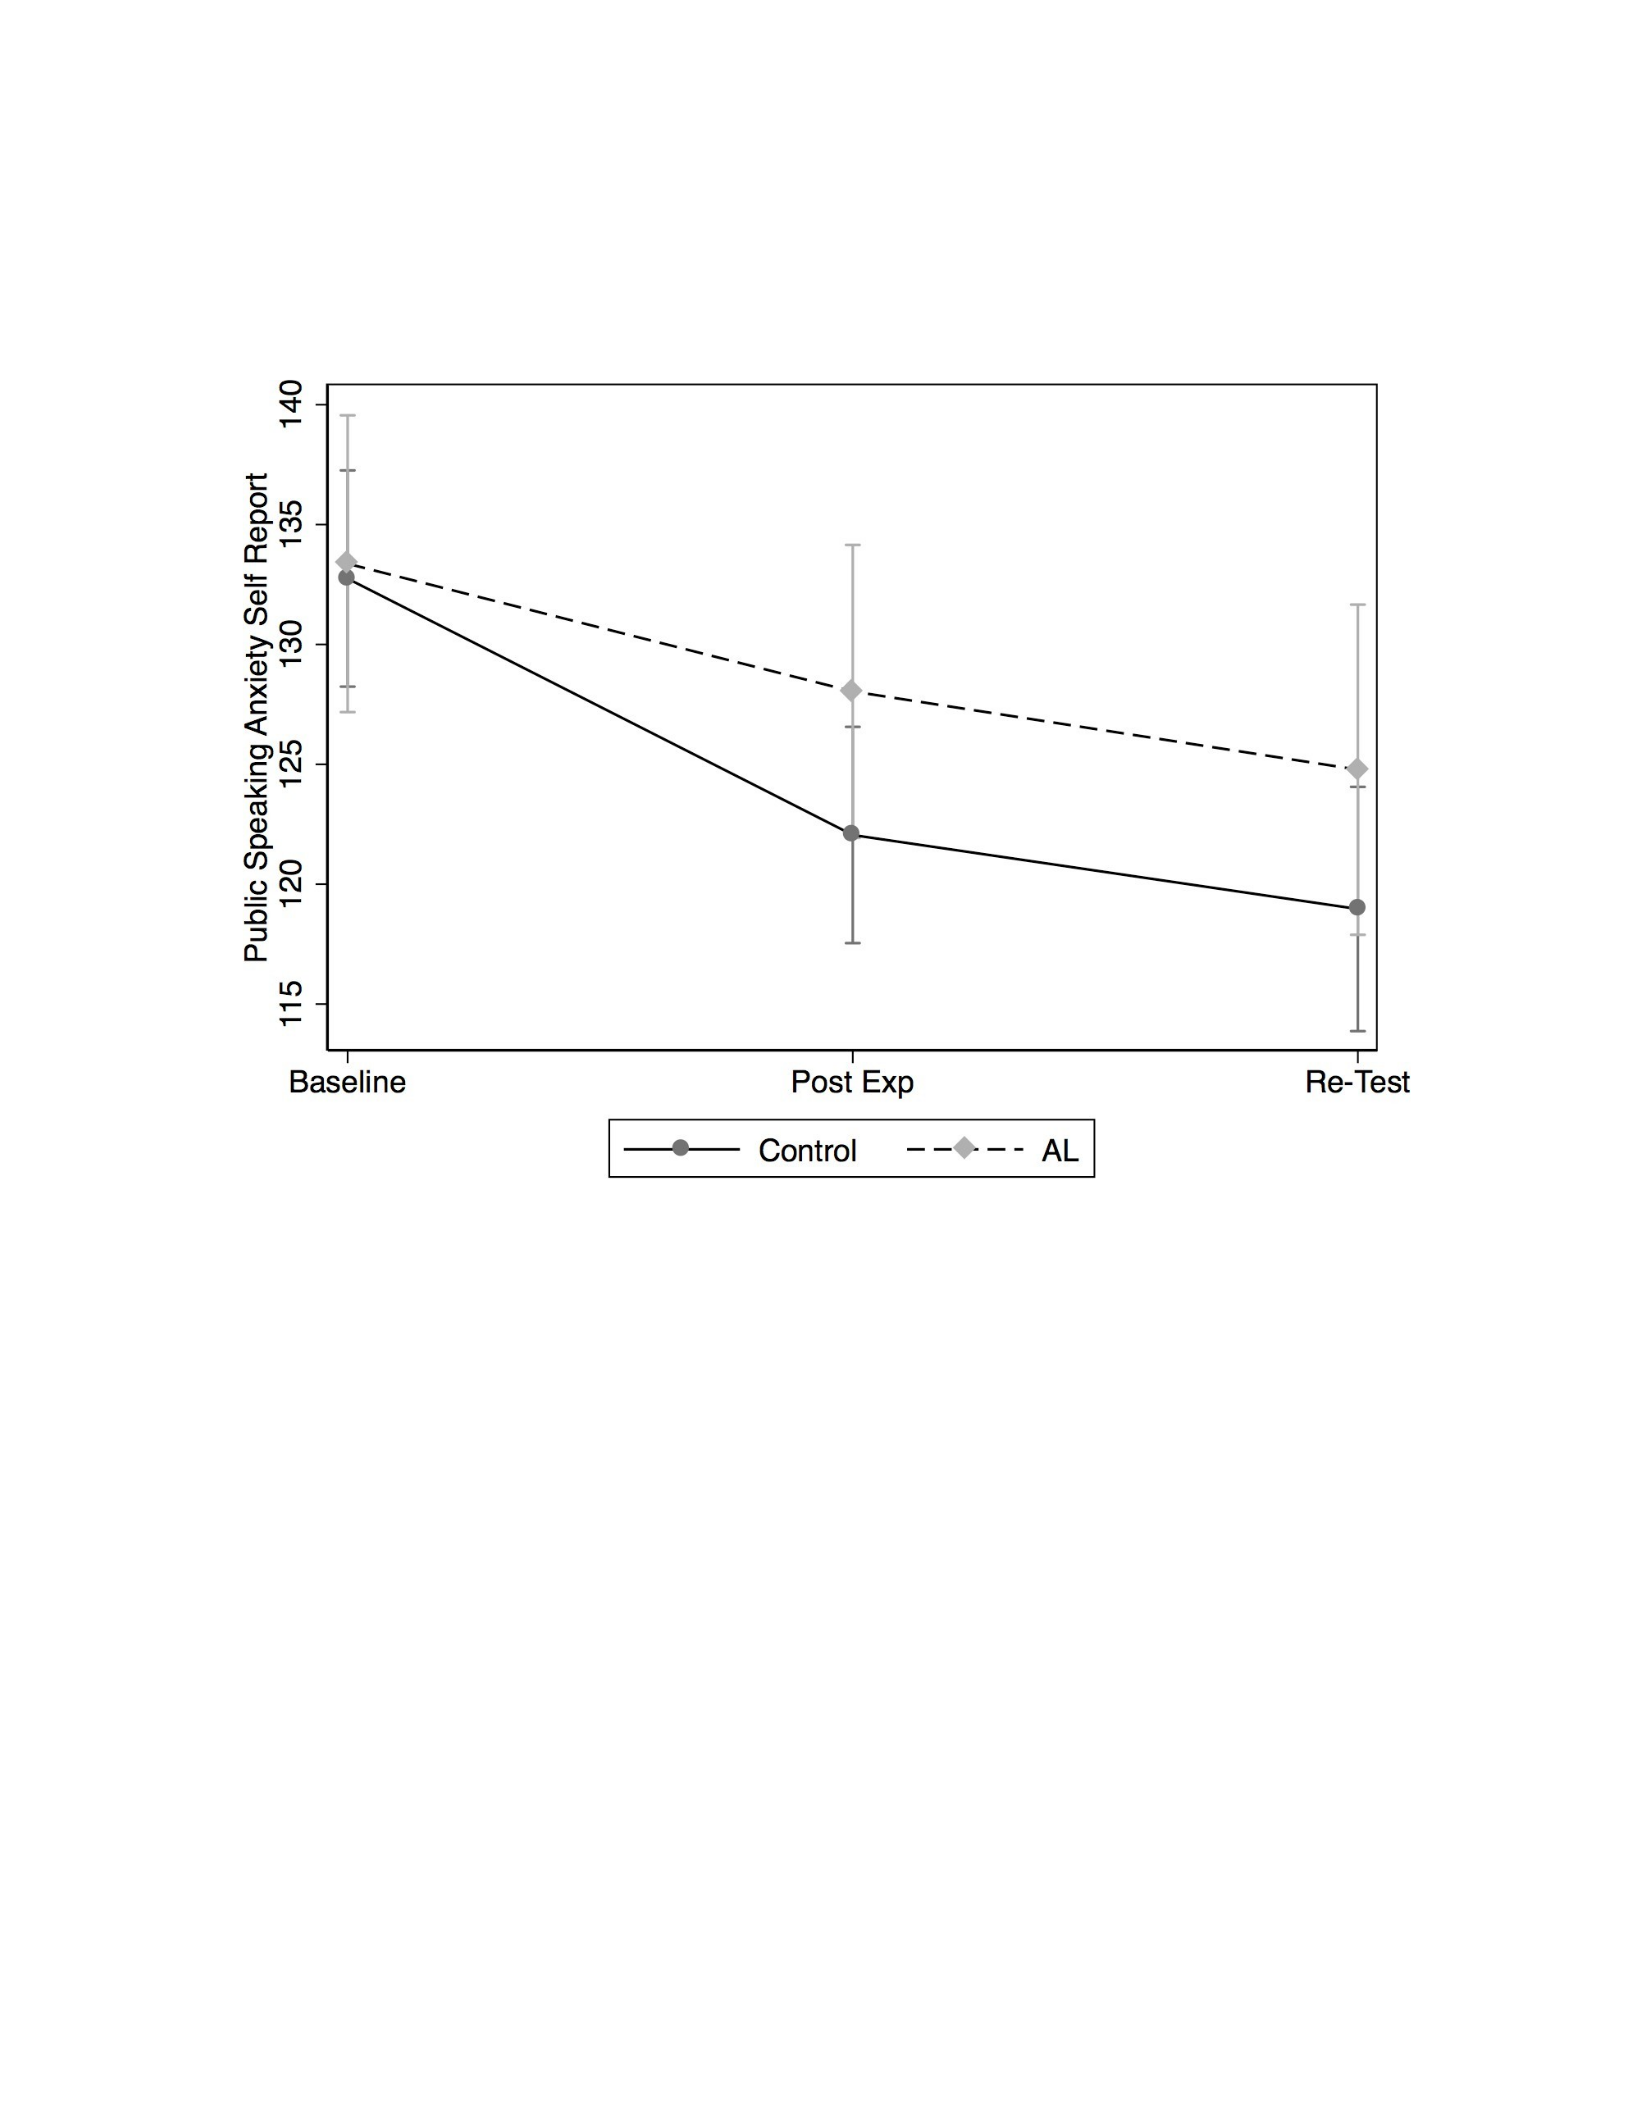
80
Figure 18. Personal Report of Public Speaking Anxiety Over Time by Group for High Labelers
Only
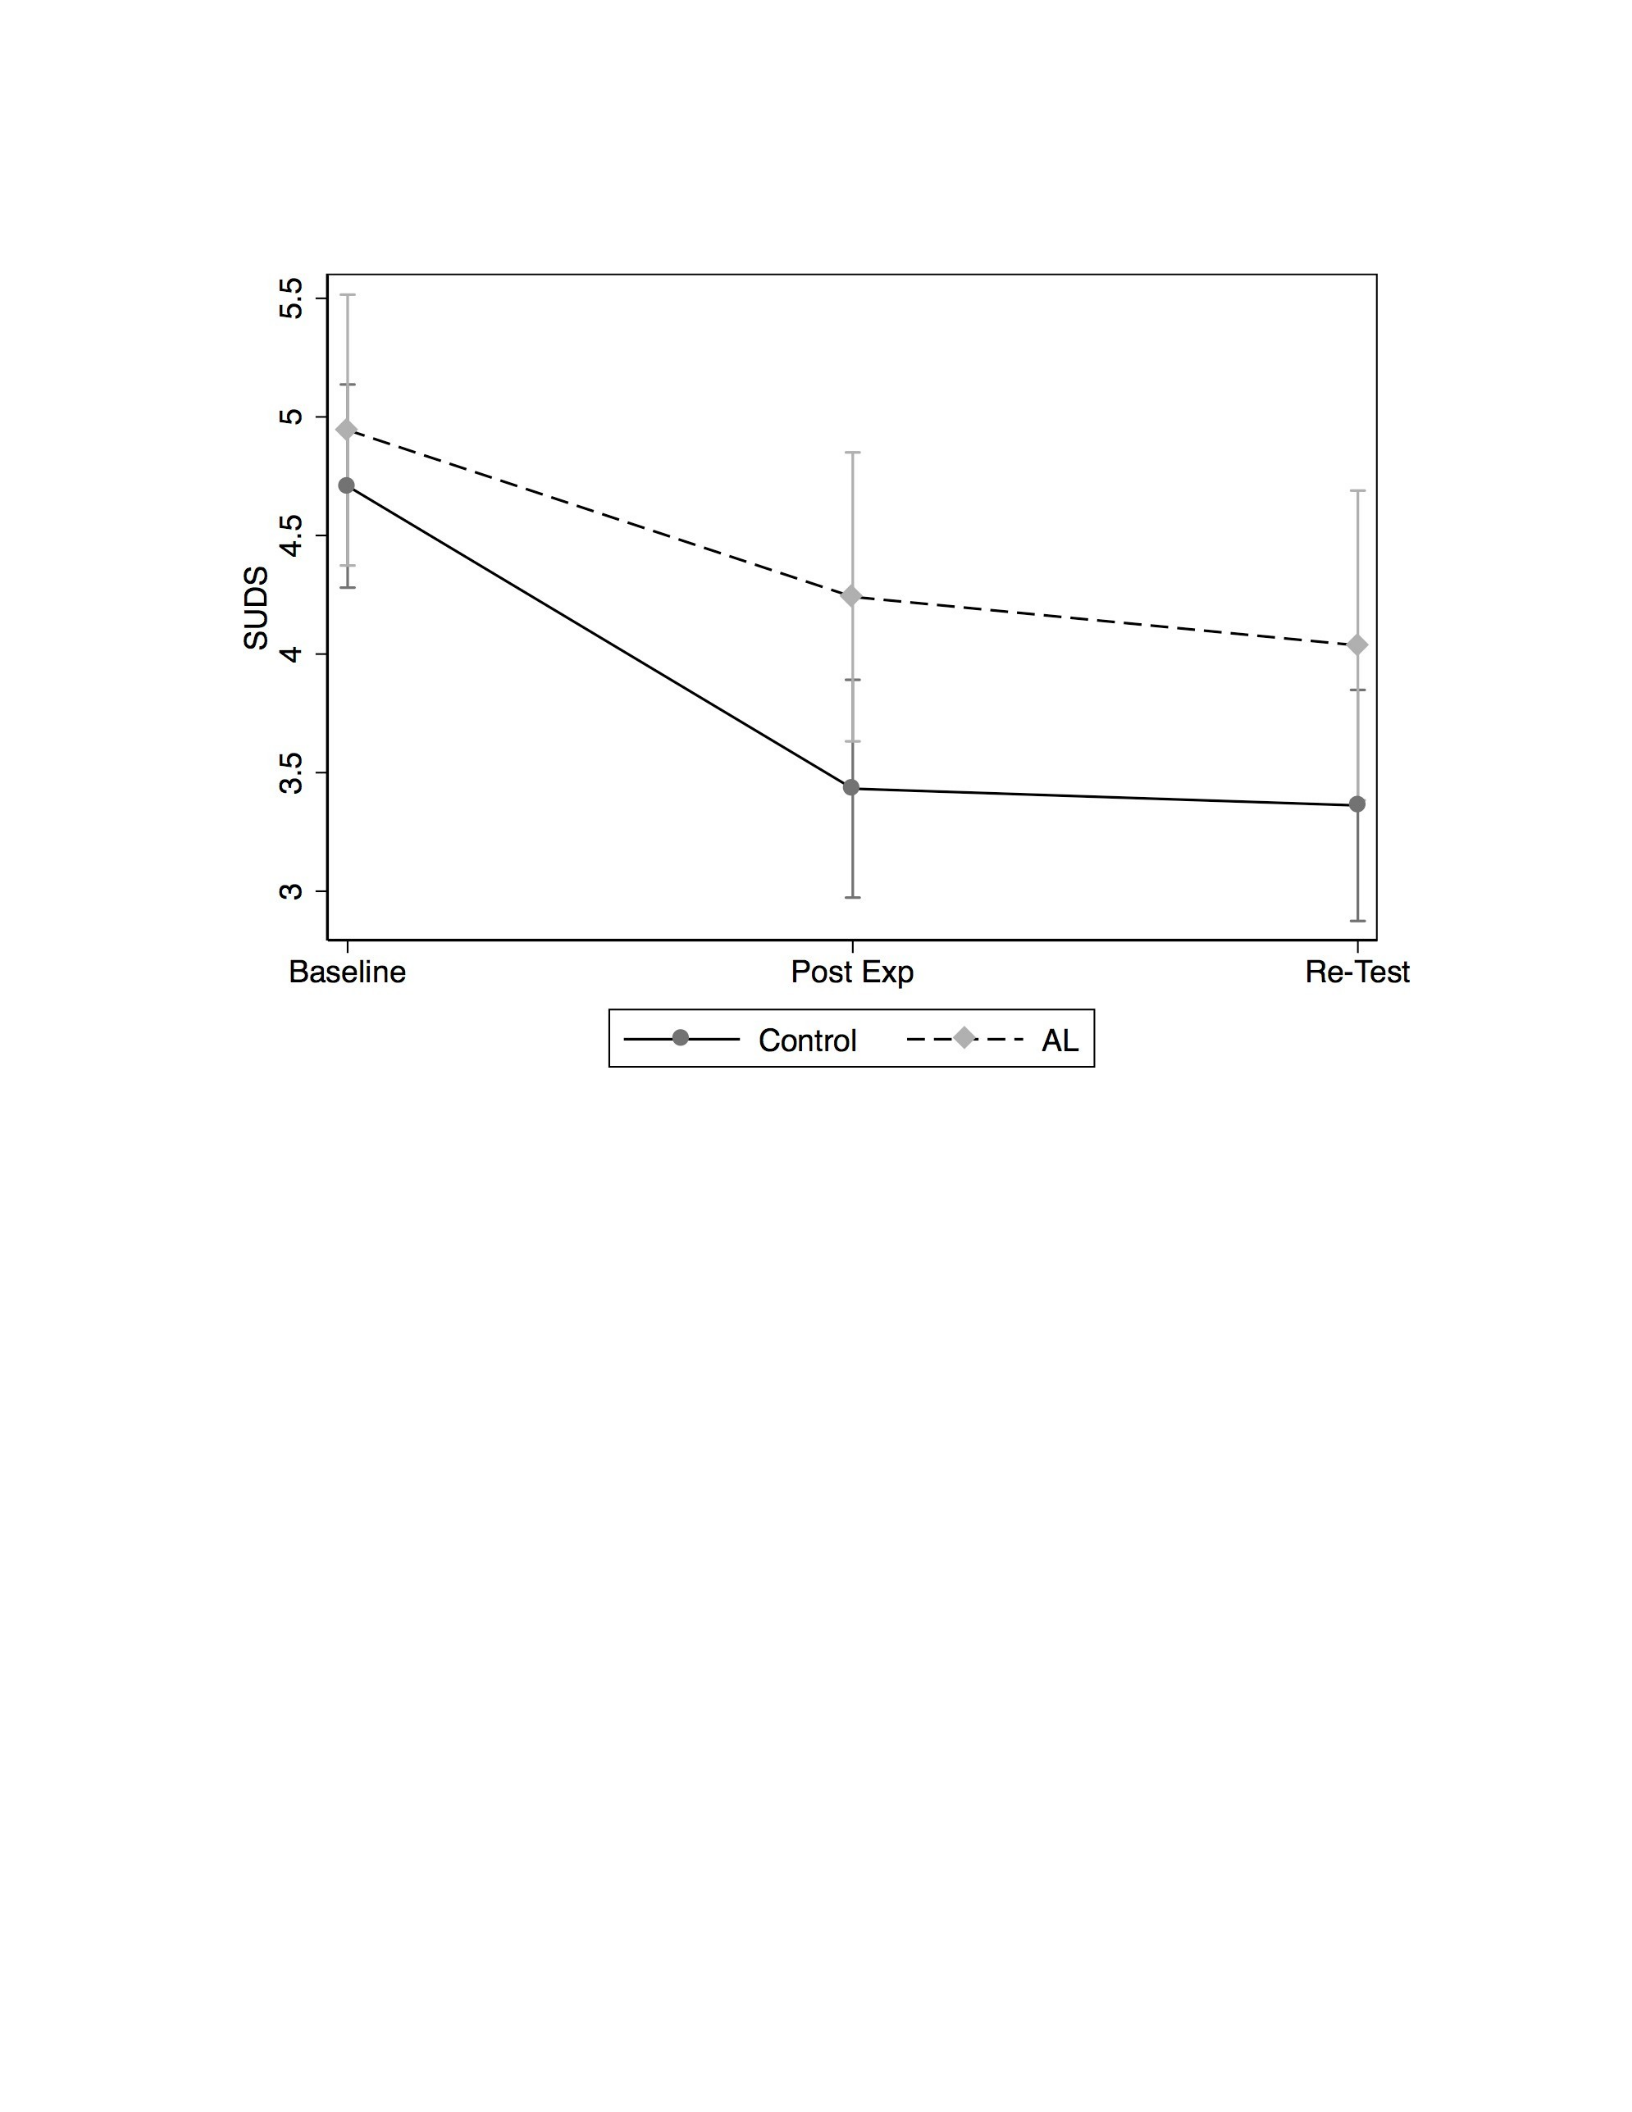
81
Figure 19. Subjective Units of Distress Over Time by Group for High Labelers Only
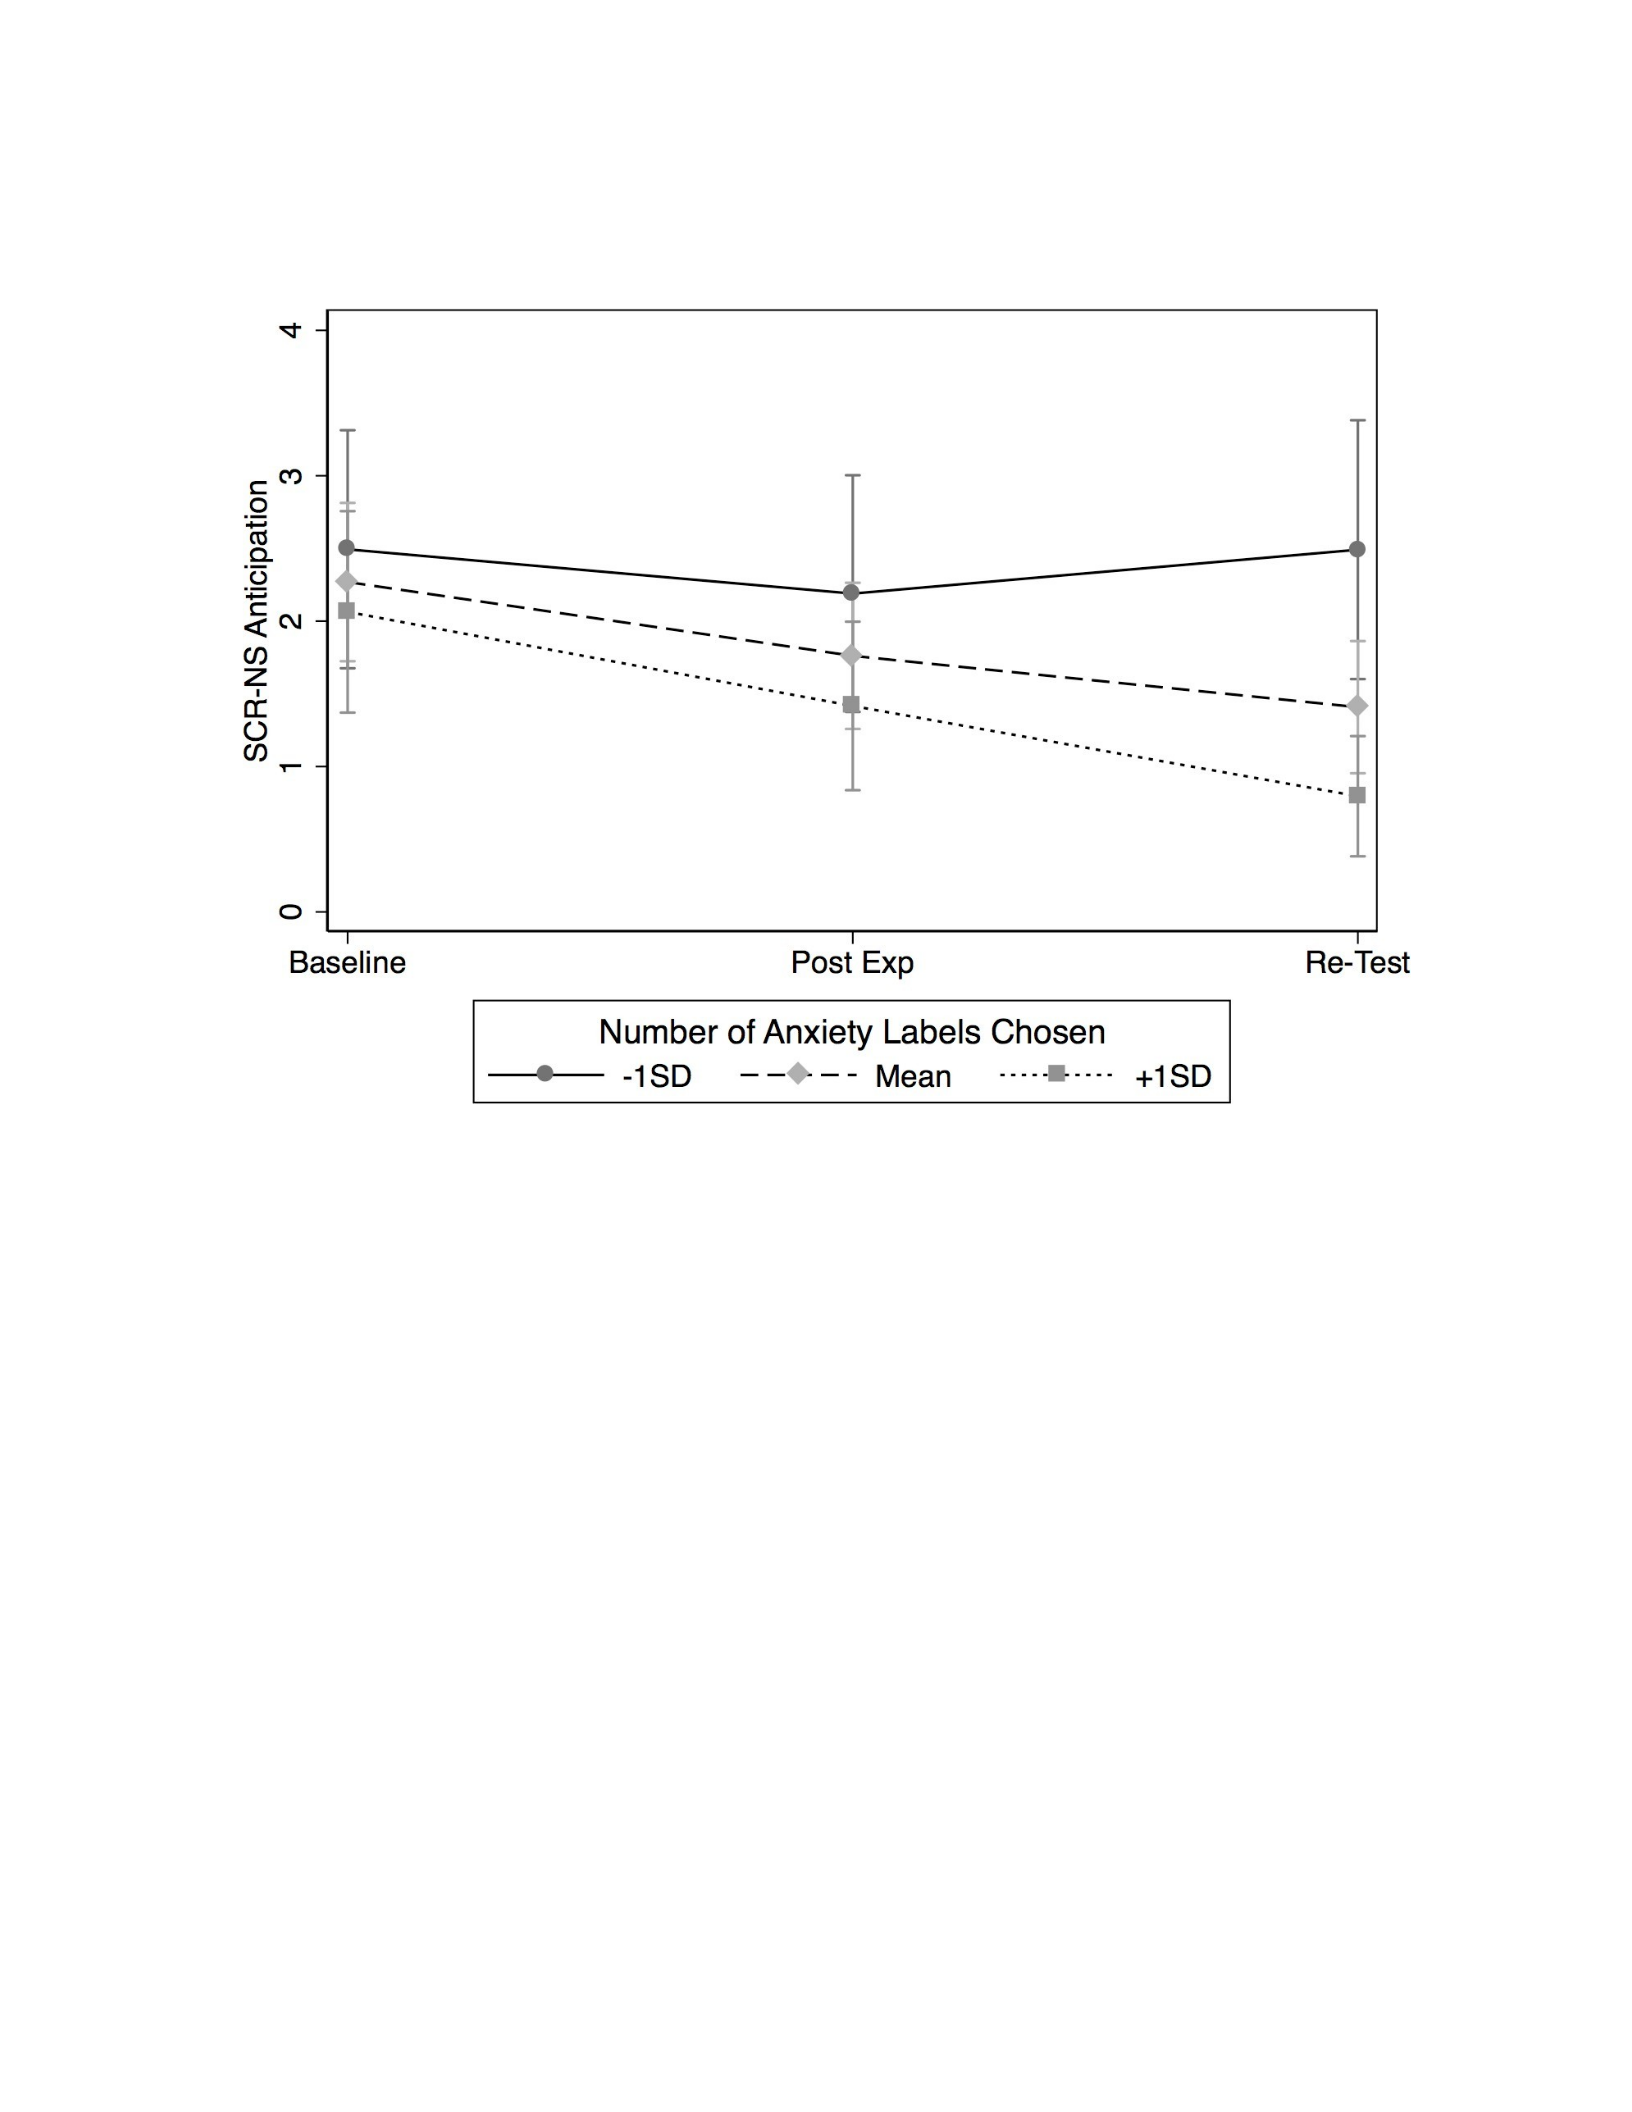
82
Figure 20. Association Between Number of Anxiety Words Chosen and Non-Specific Skin
Conductance Response during Anticipation over Time
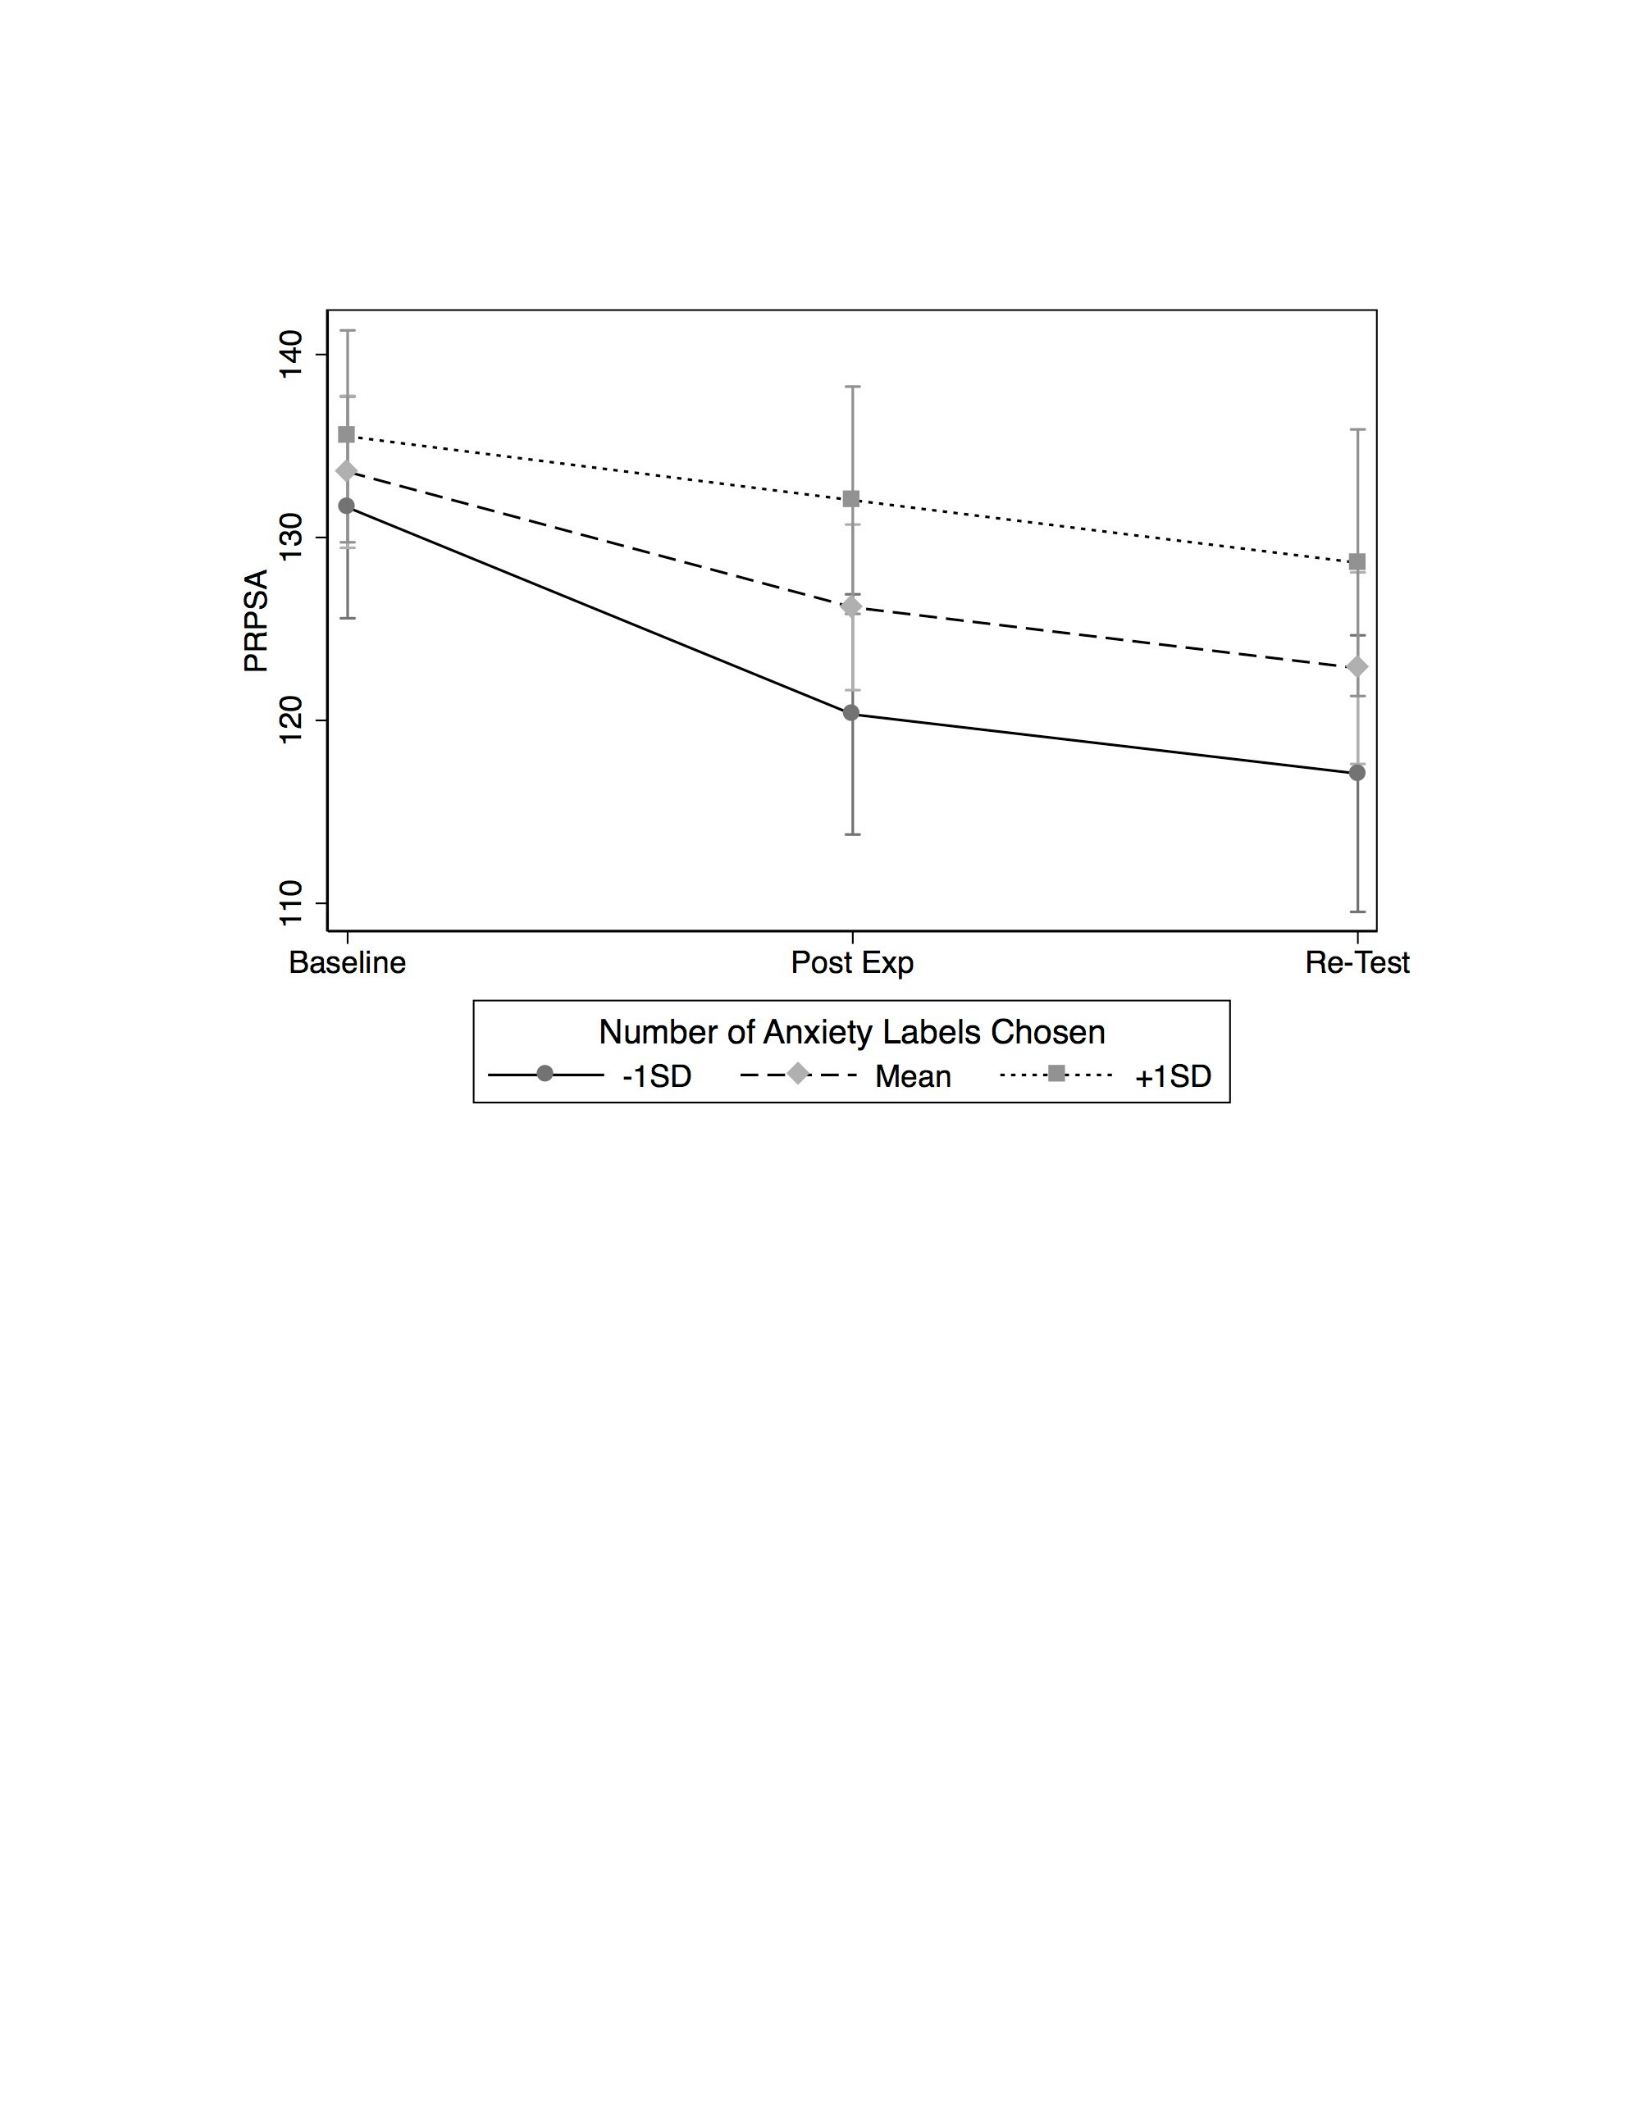
83
Figure 21. Association Between Number of Anxiety Words Chosen and Personal Report of
Public Speaking Anxiety Over Time
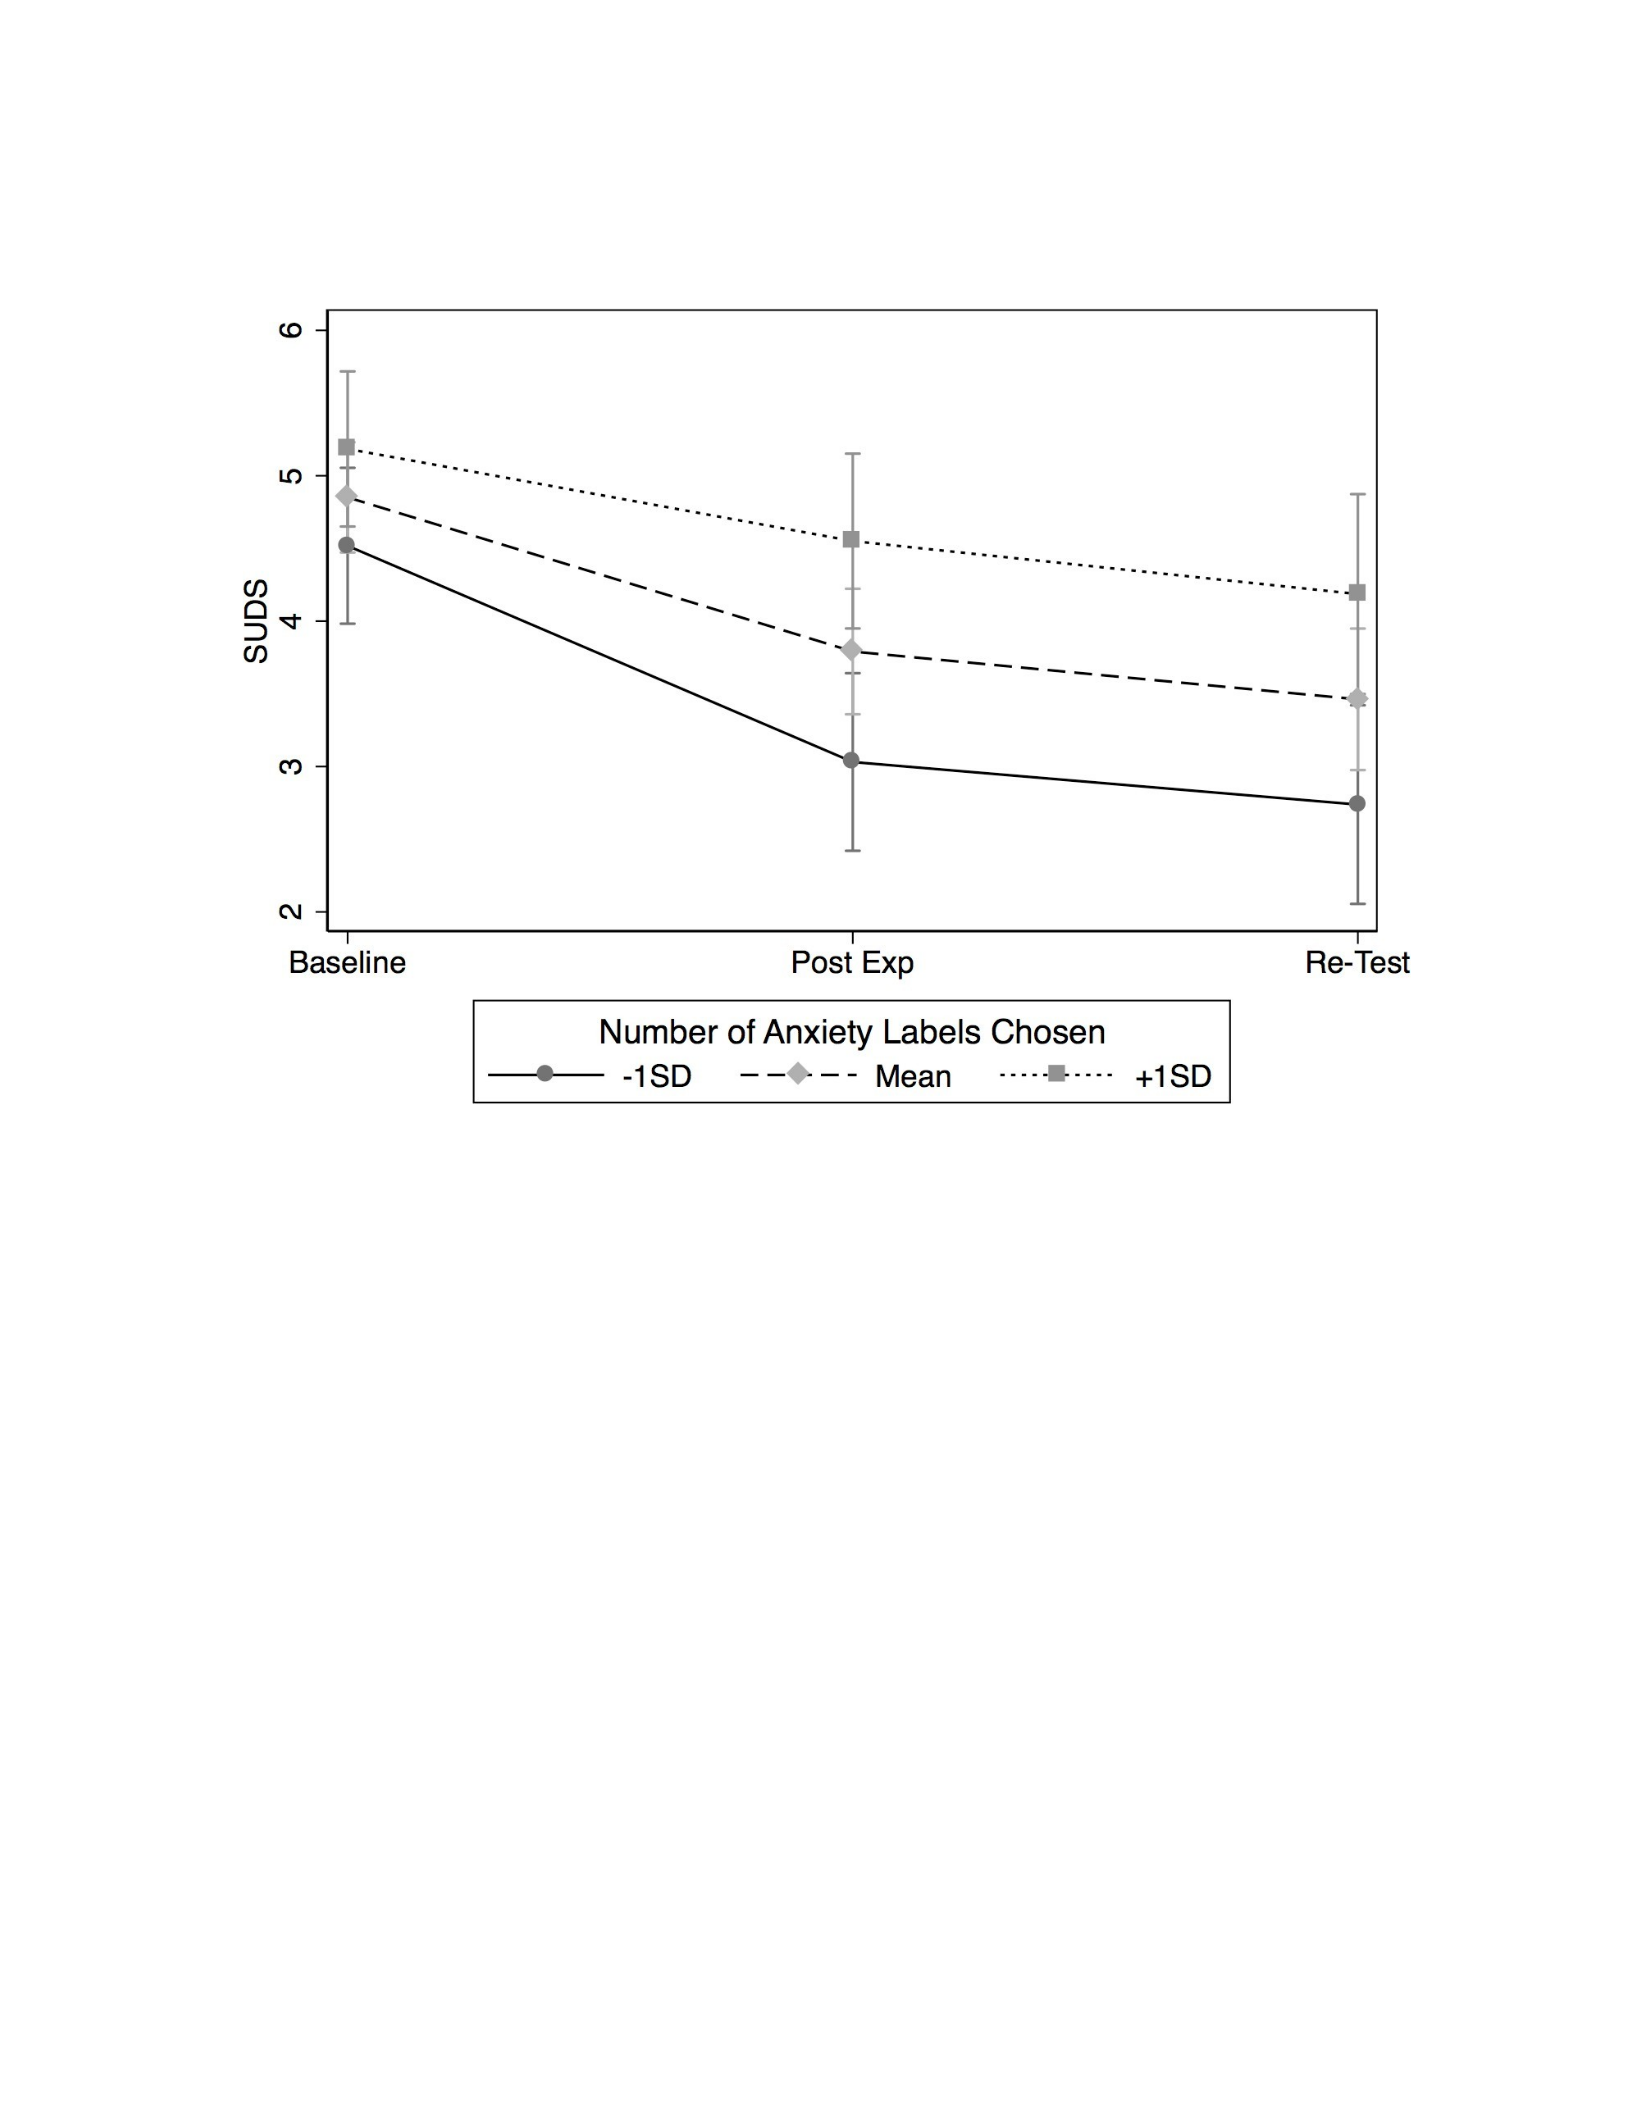
84
Figure 22. Association Between Number of Anxiety Words Chosen and Subjective Units of
Distress Over Time
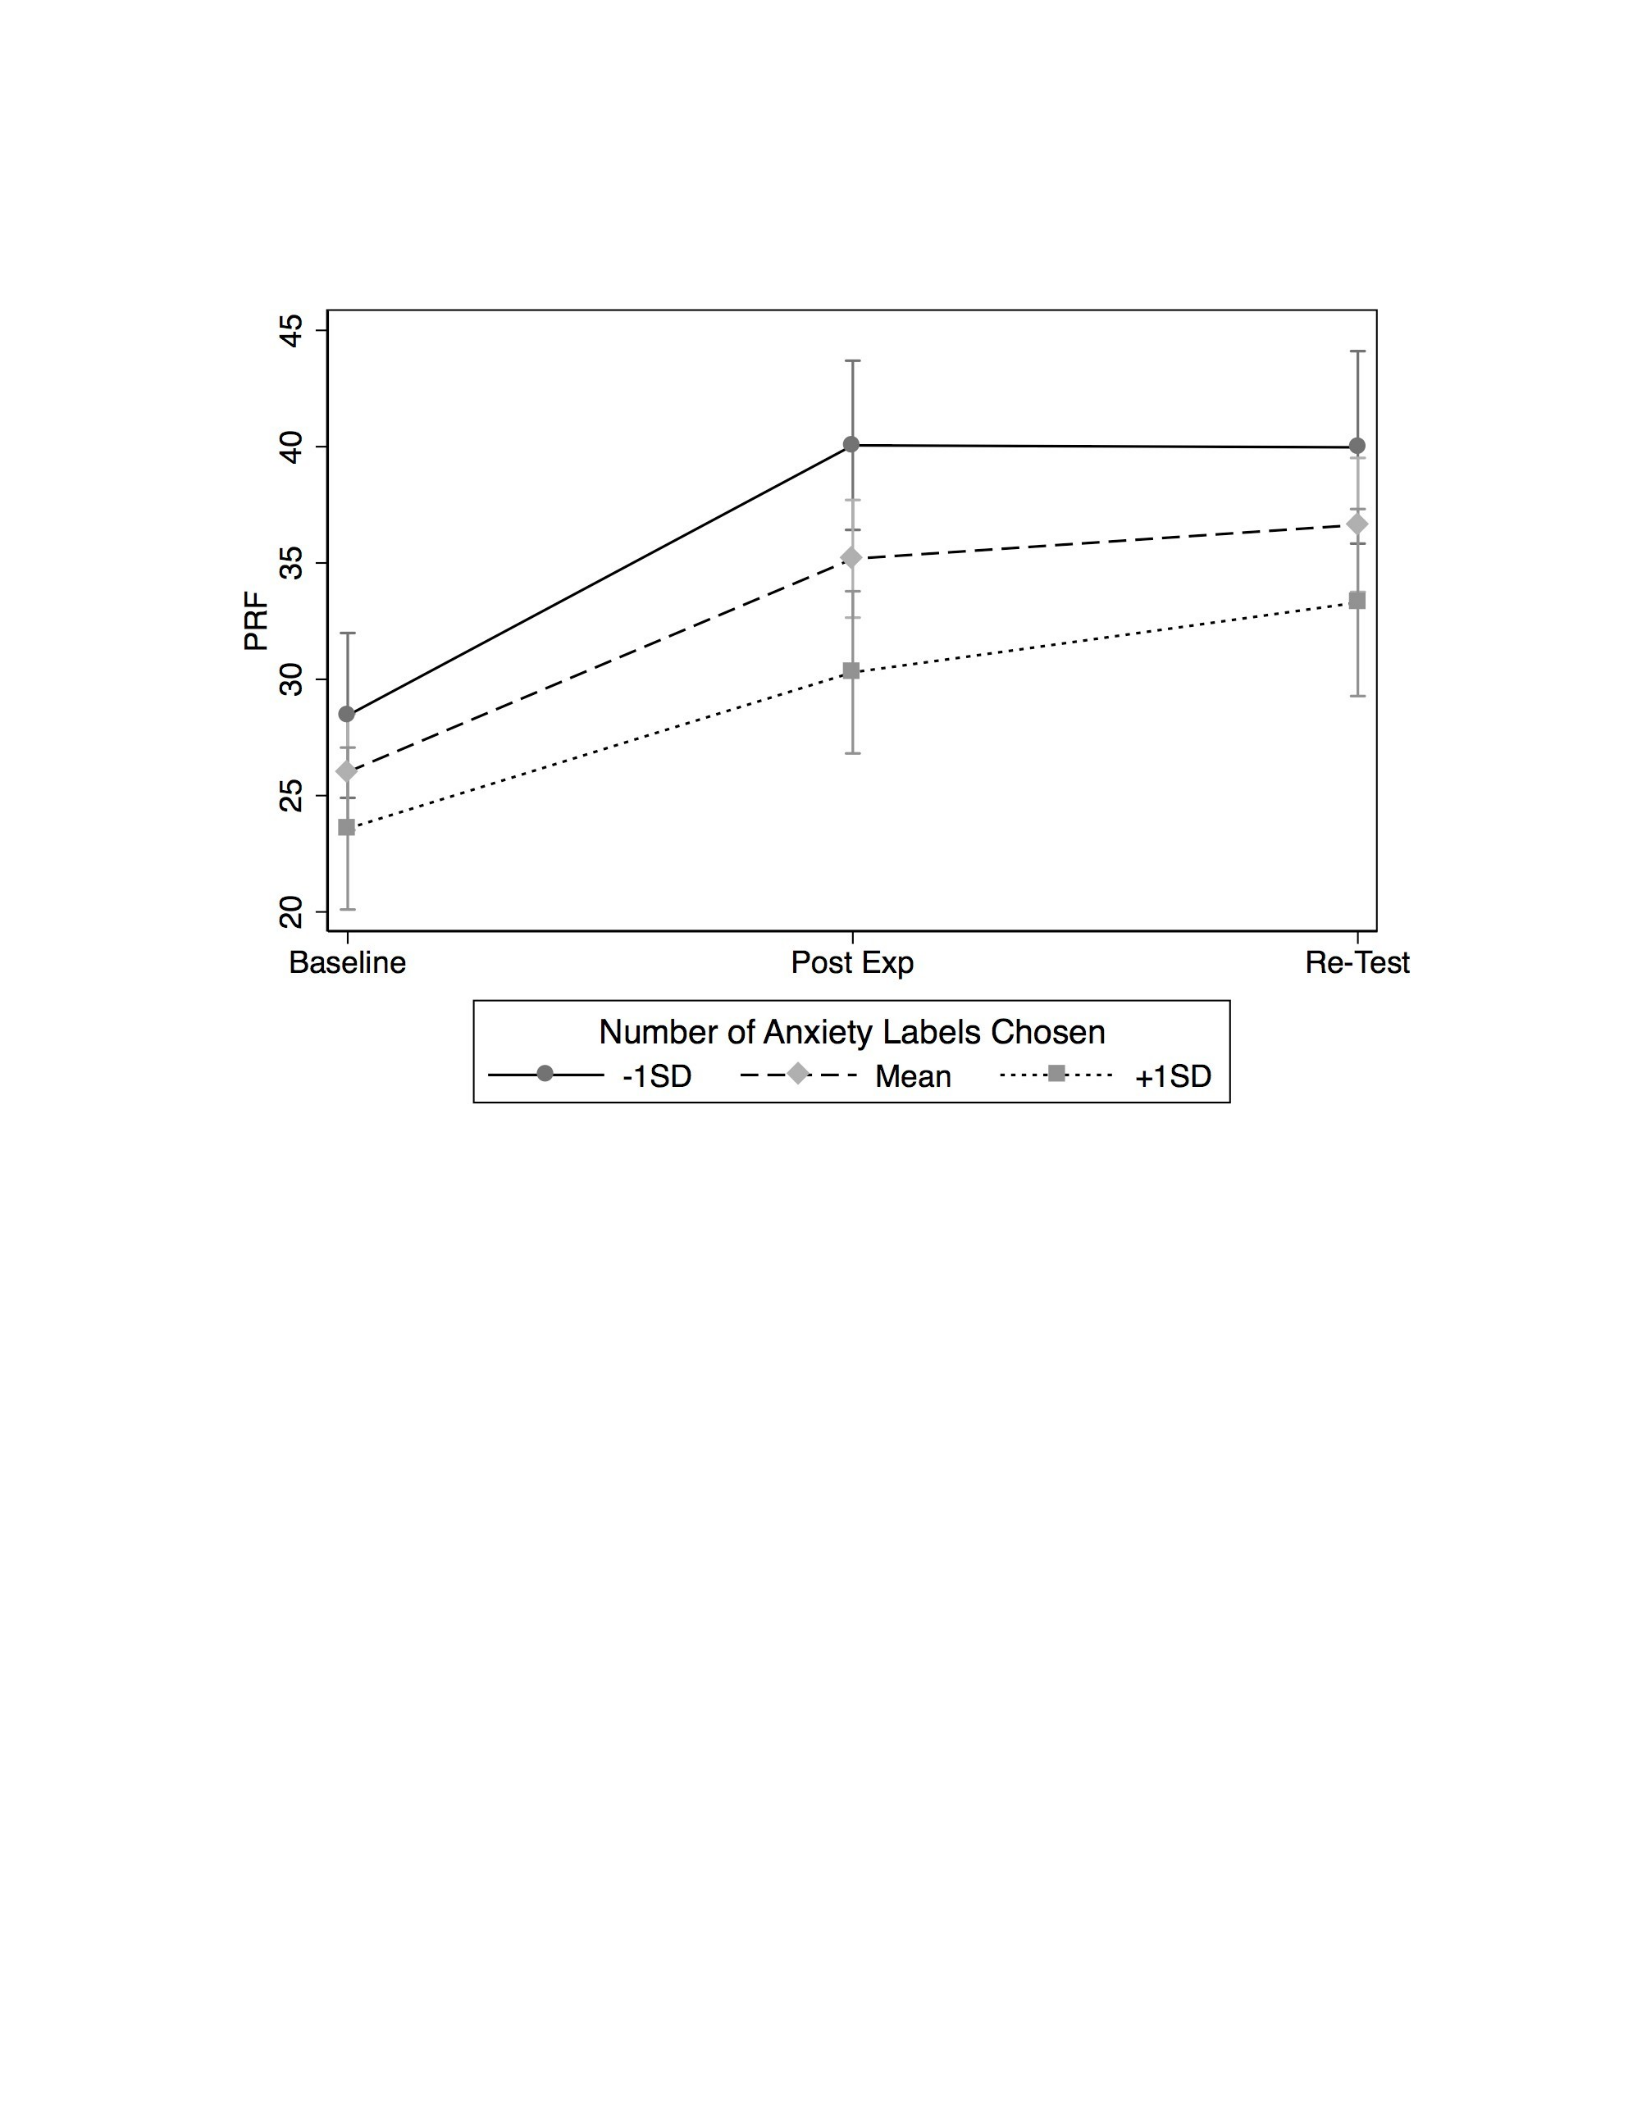
85
Figure 23. Association Between Number of Anxiety Words Chosen and Performance Rating
Form Over Time
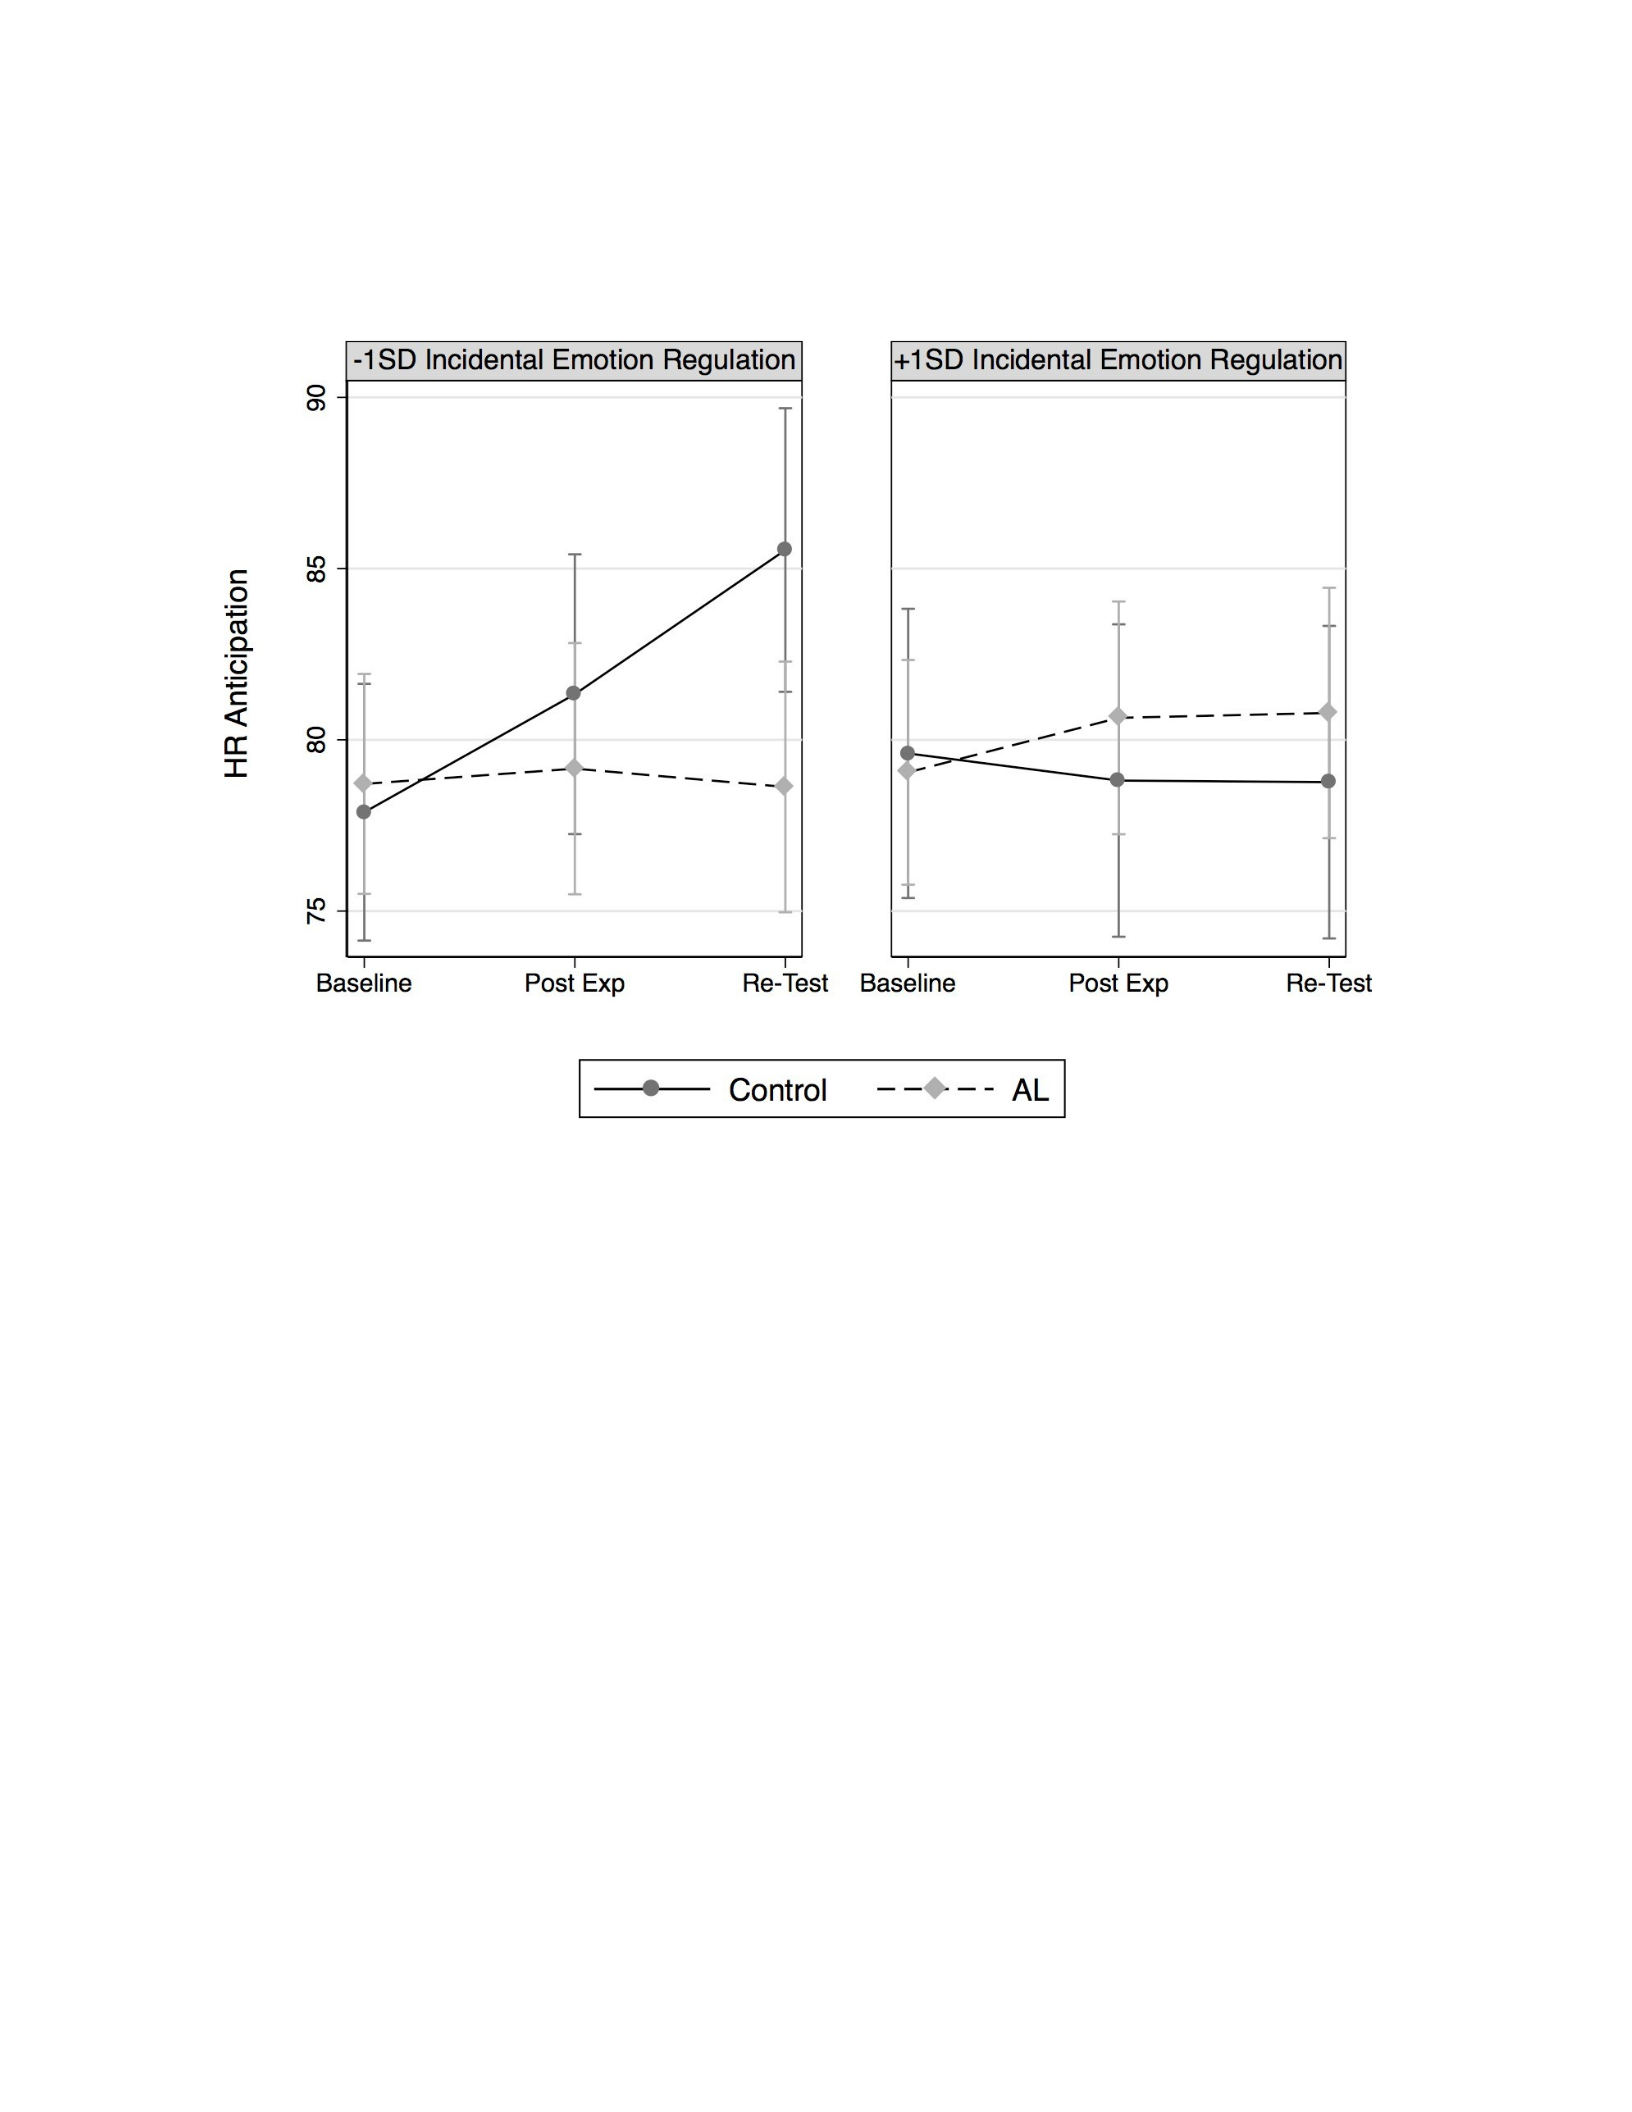
86
Figure 24. Moderation of Heart Rate during anticipation over Time by Incidental Emotion
Regulation and Group
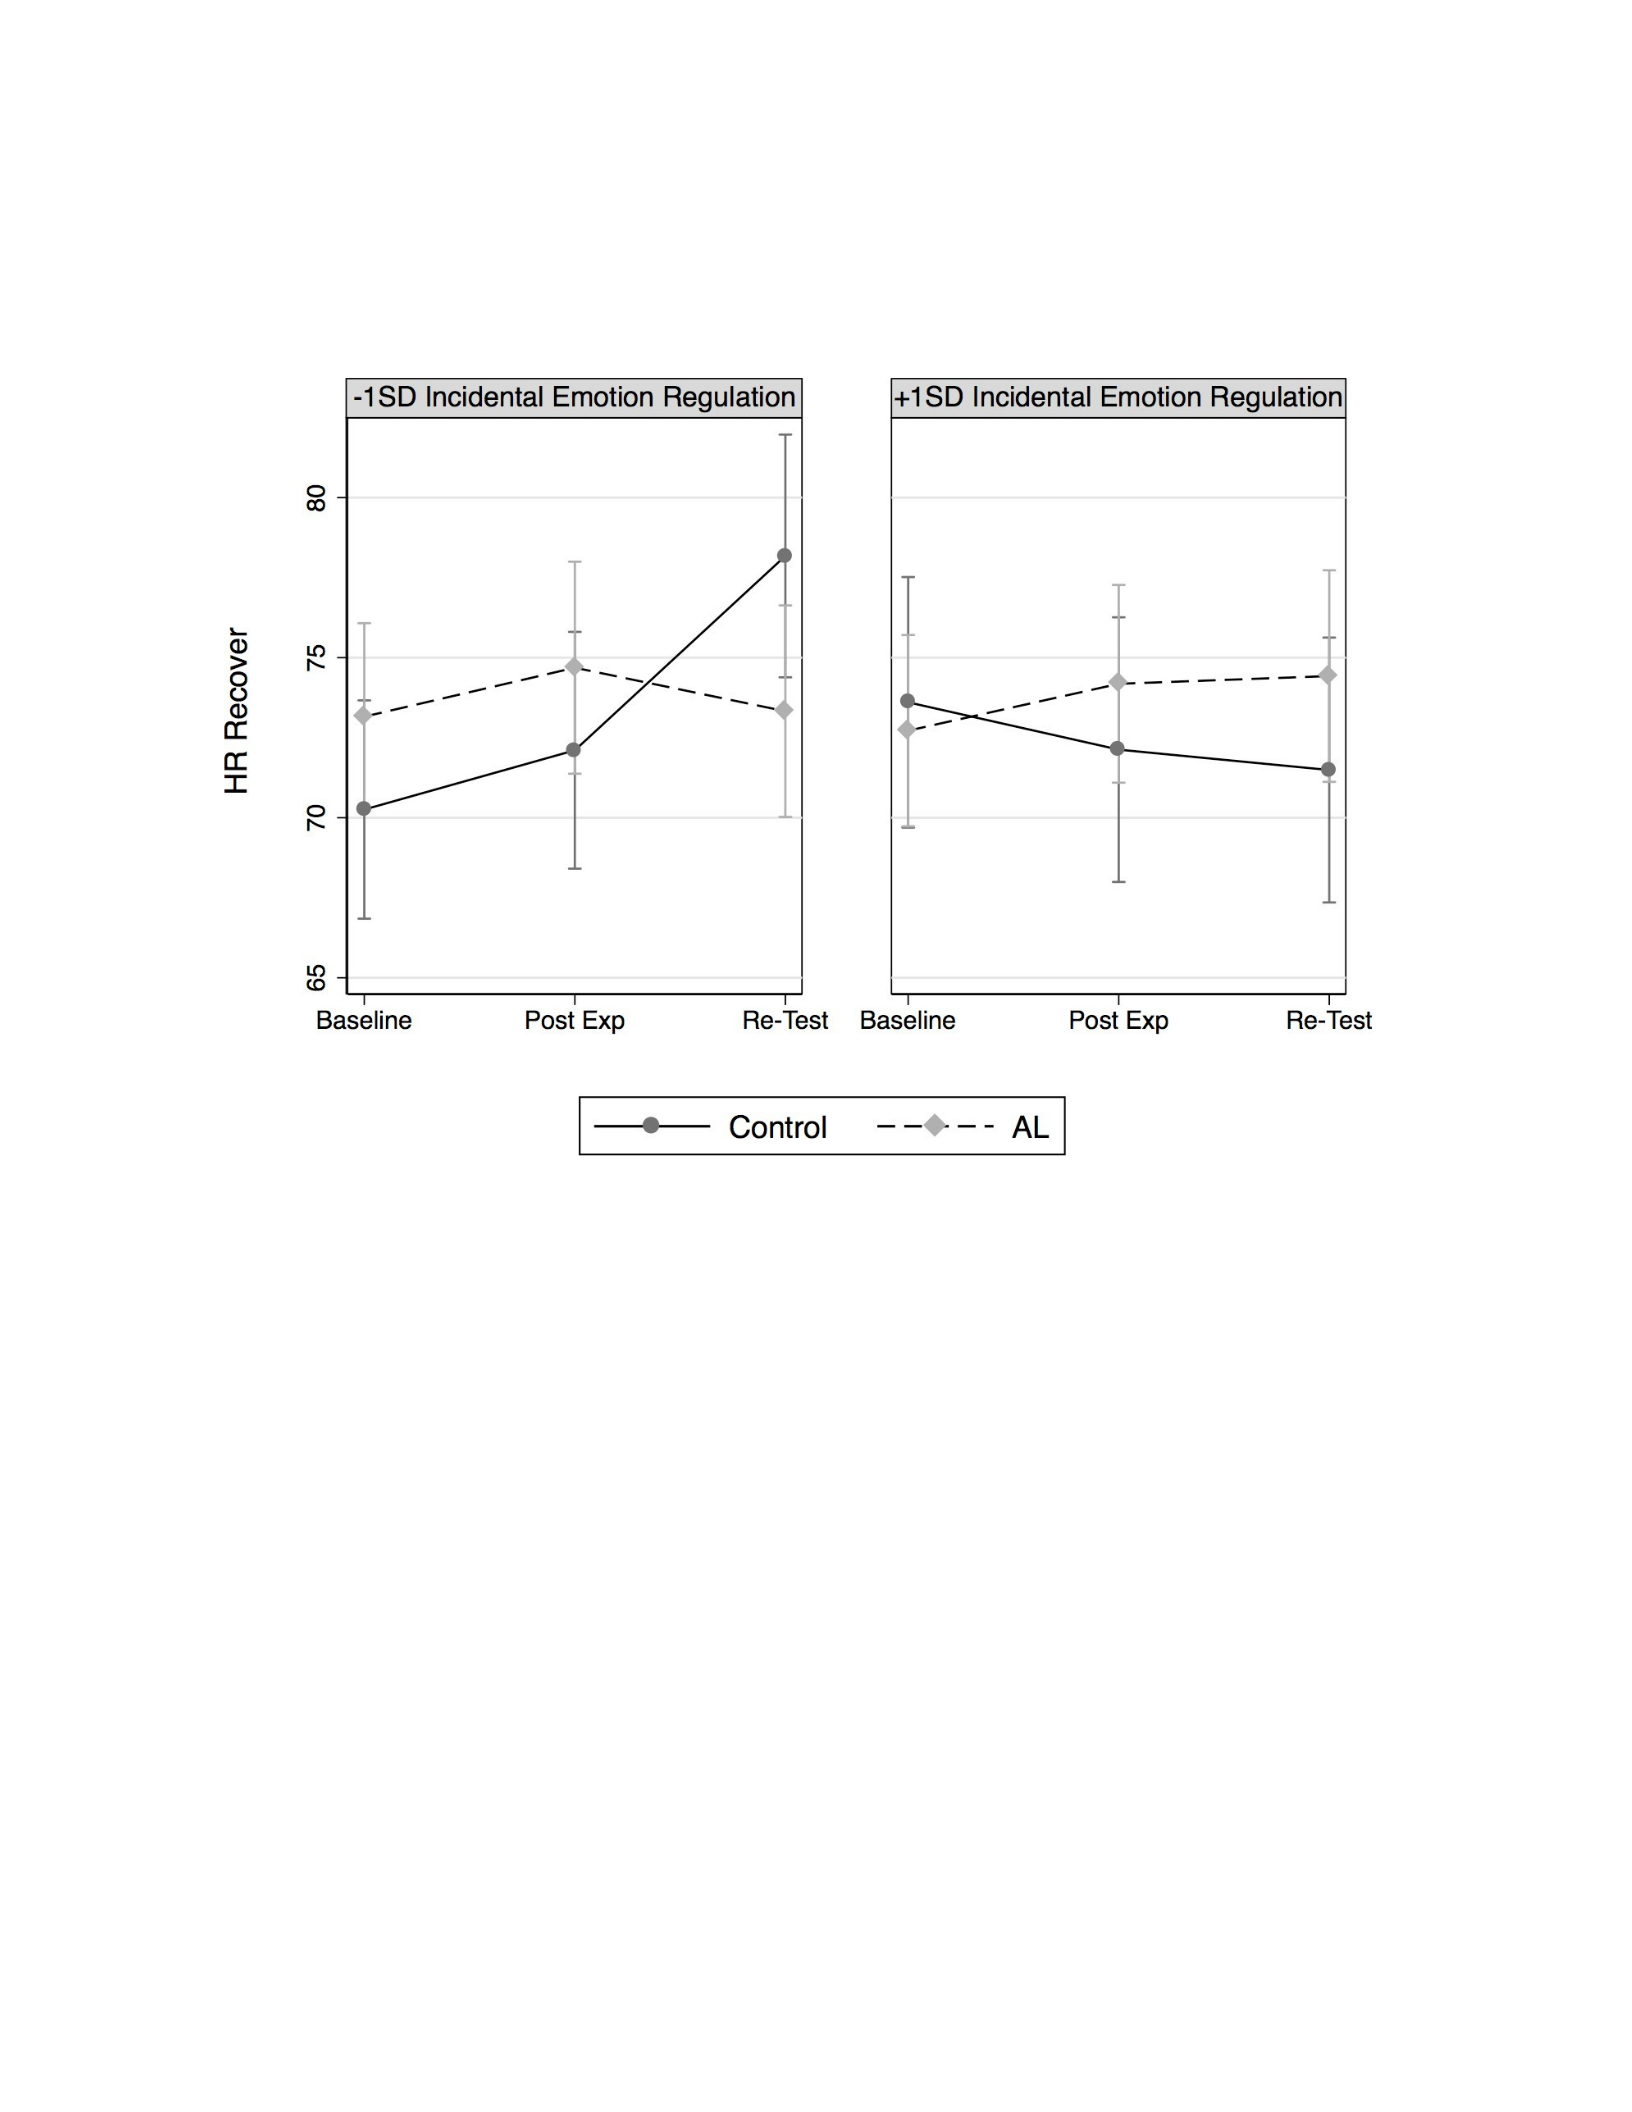
87
Figure 25. Moderation of Heart Rate during recovery over Time by Incidental Emotion
Regulation and Group
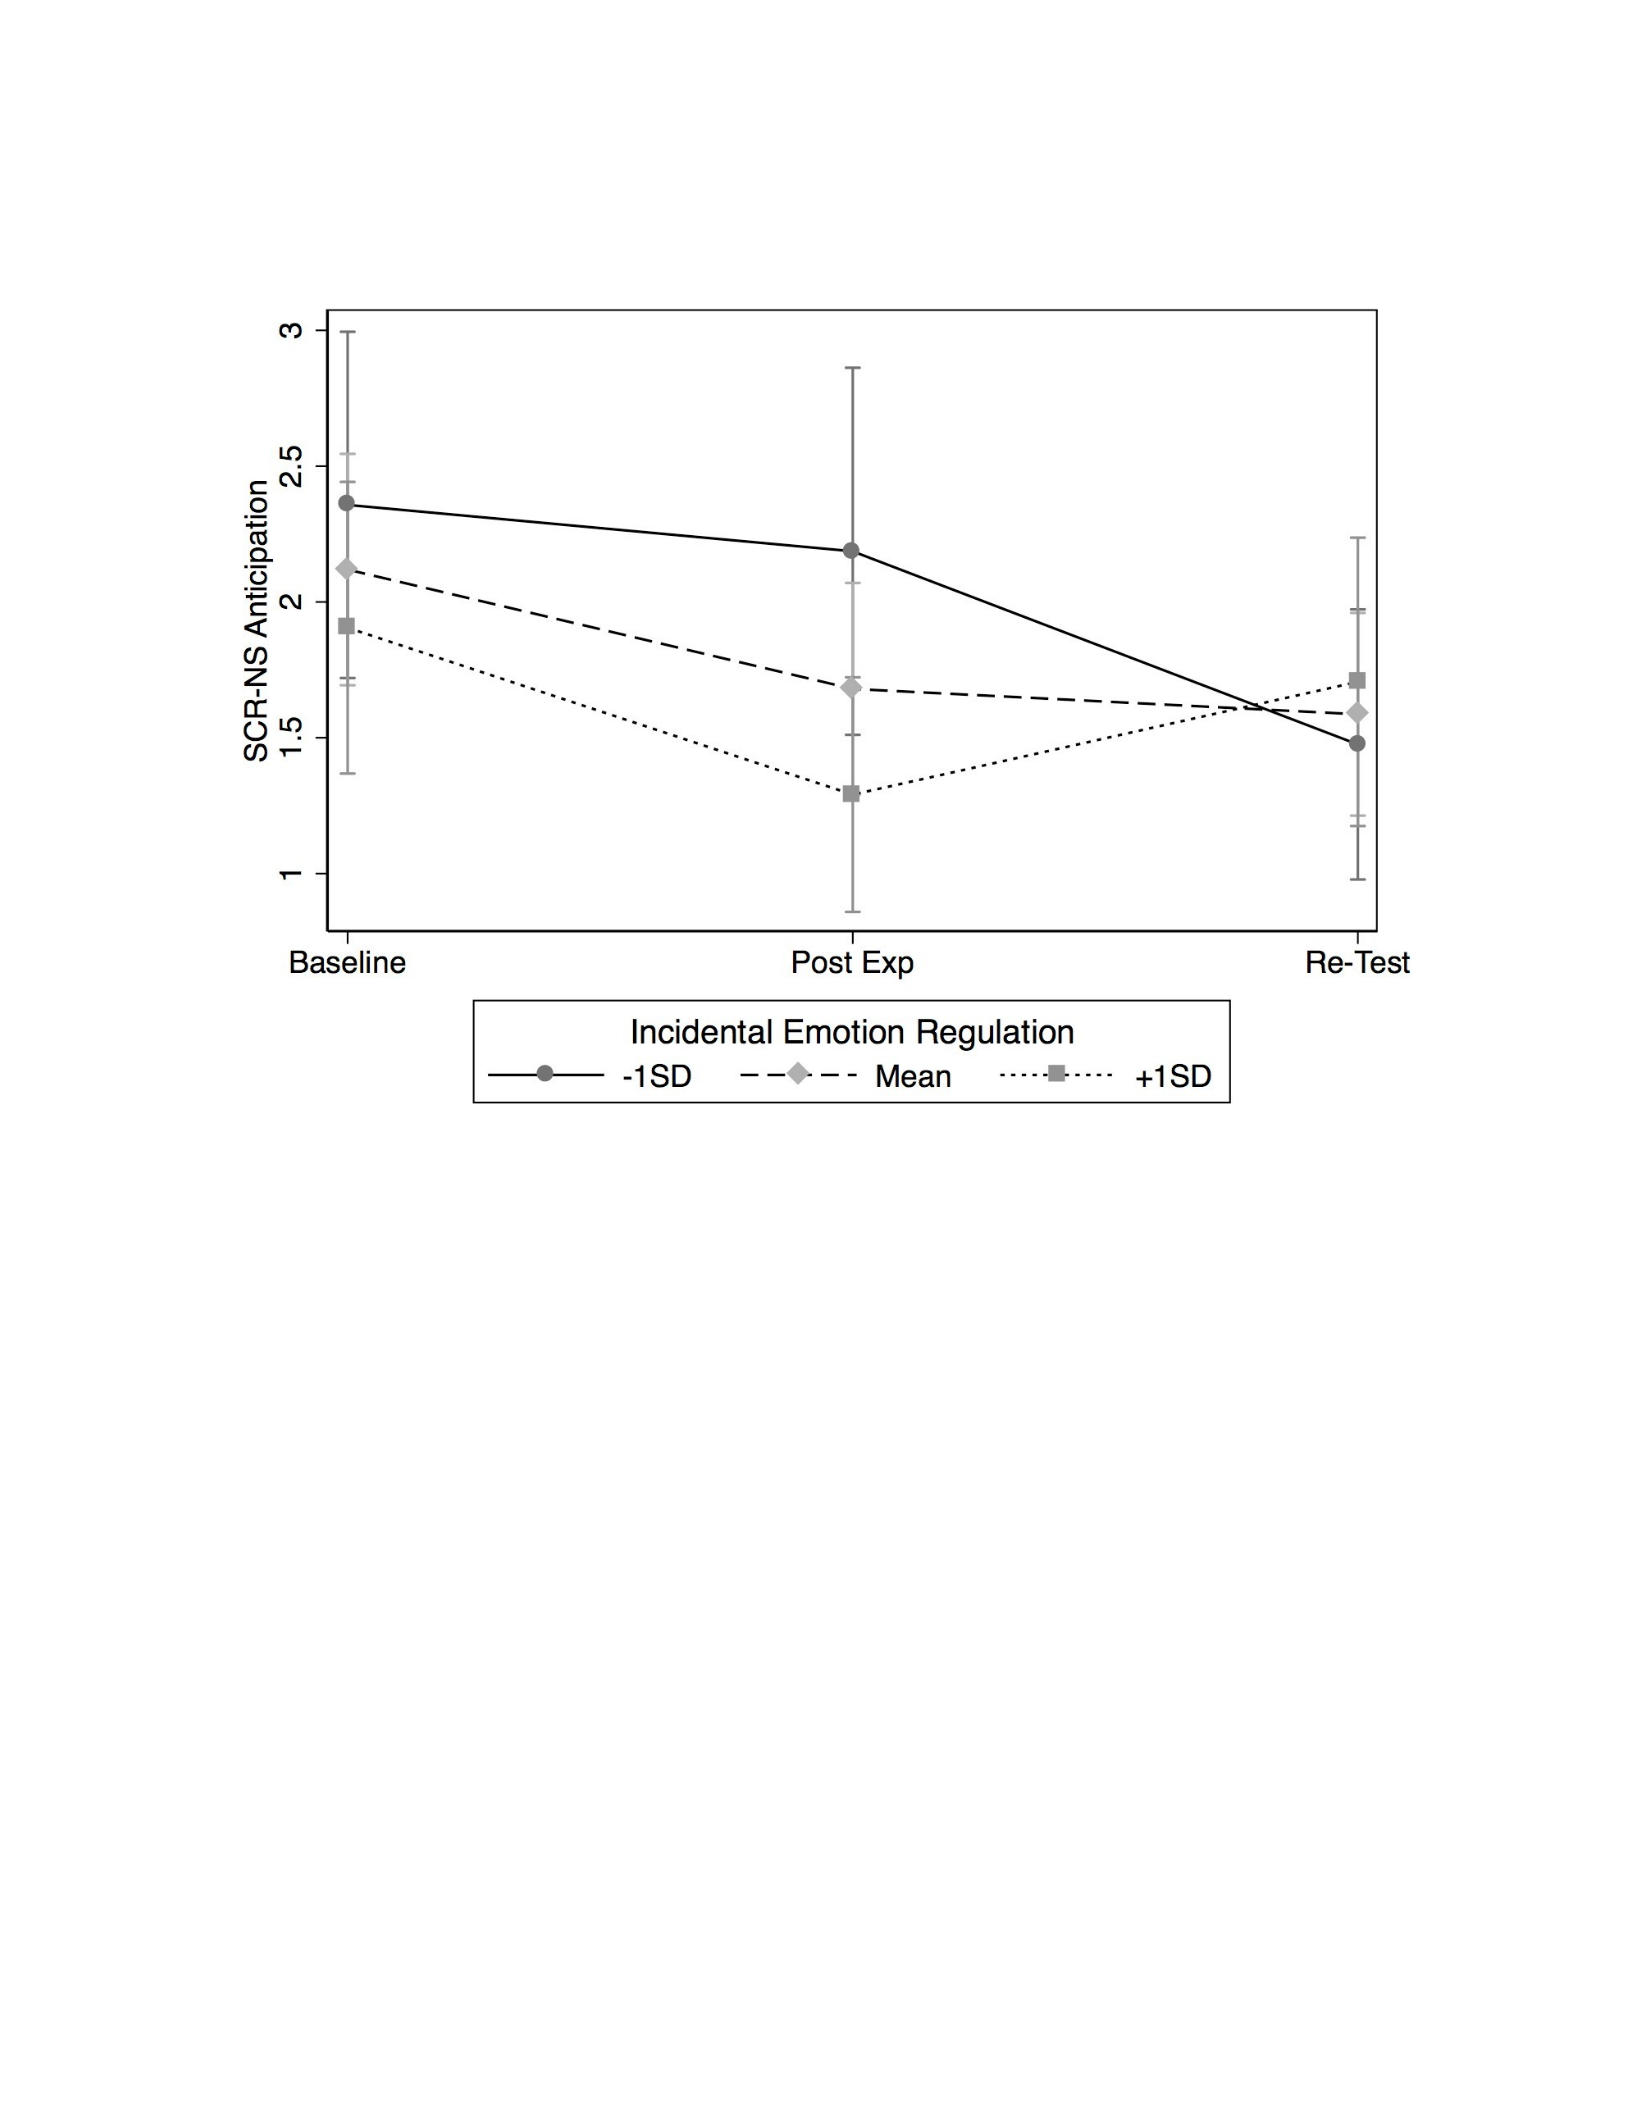
88
Figure 26. Prediction of Non-Specific Skin Conductance Response during anticipation over
Time by Incidental Emotion Regulation
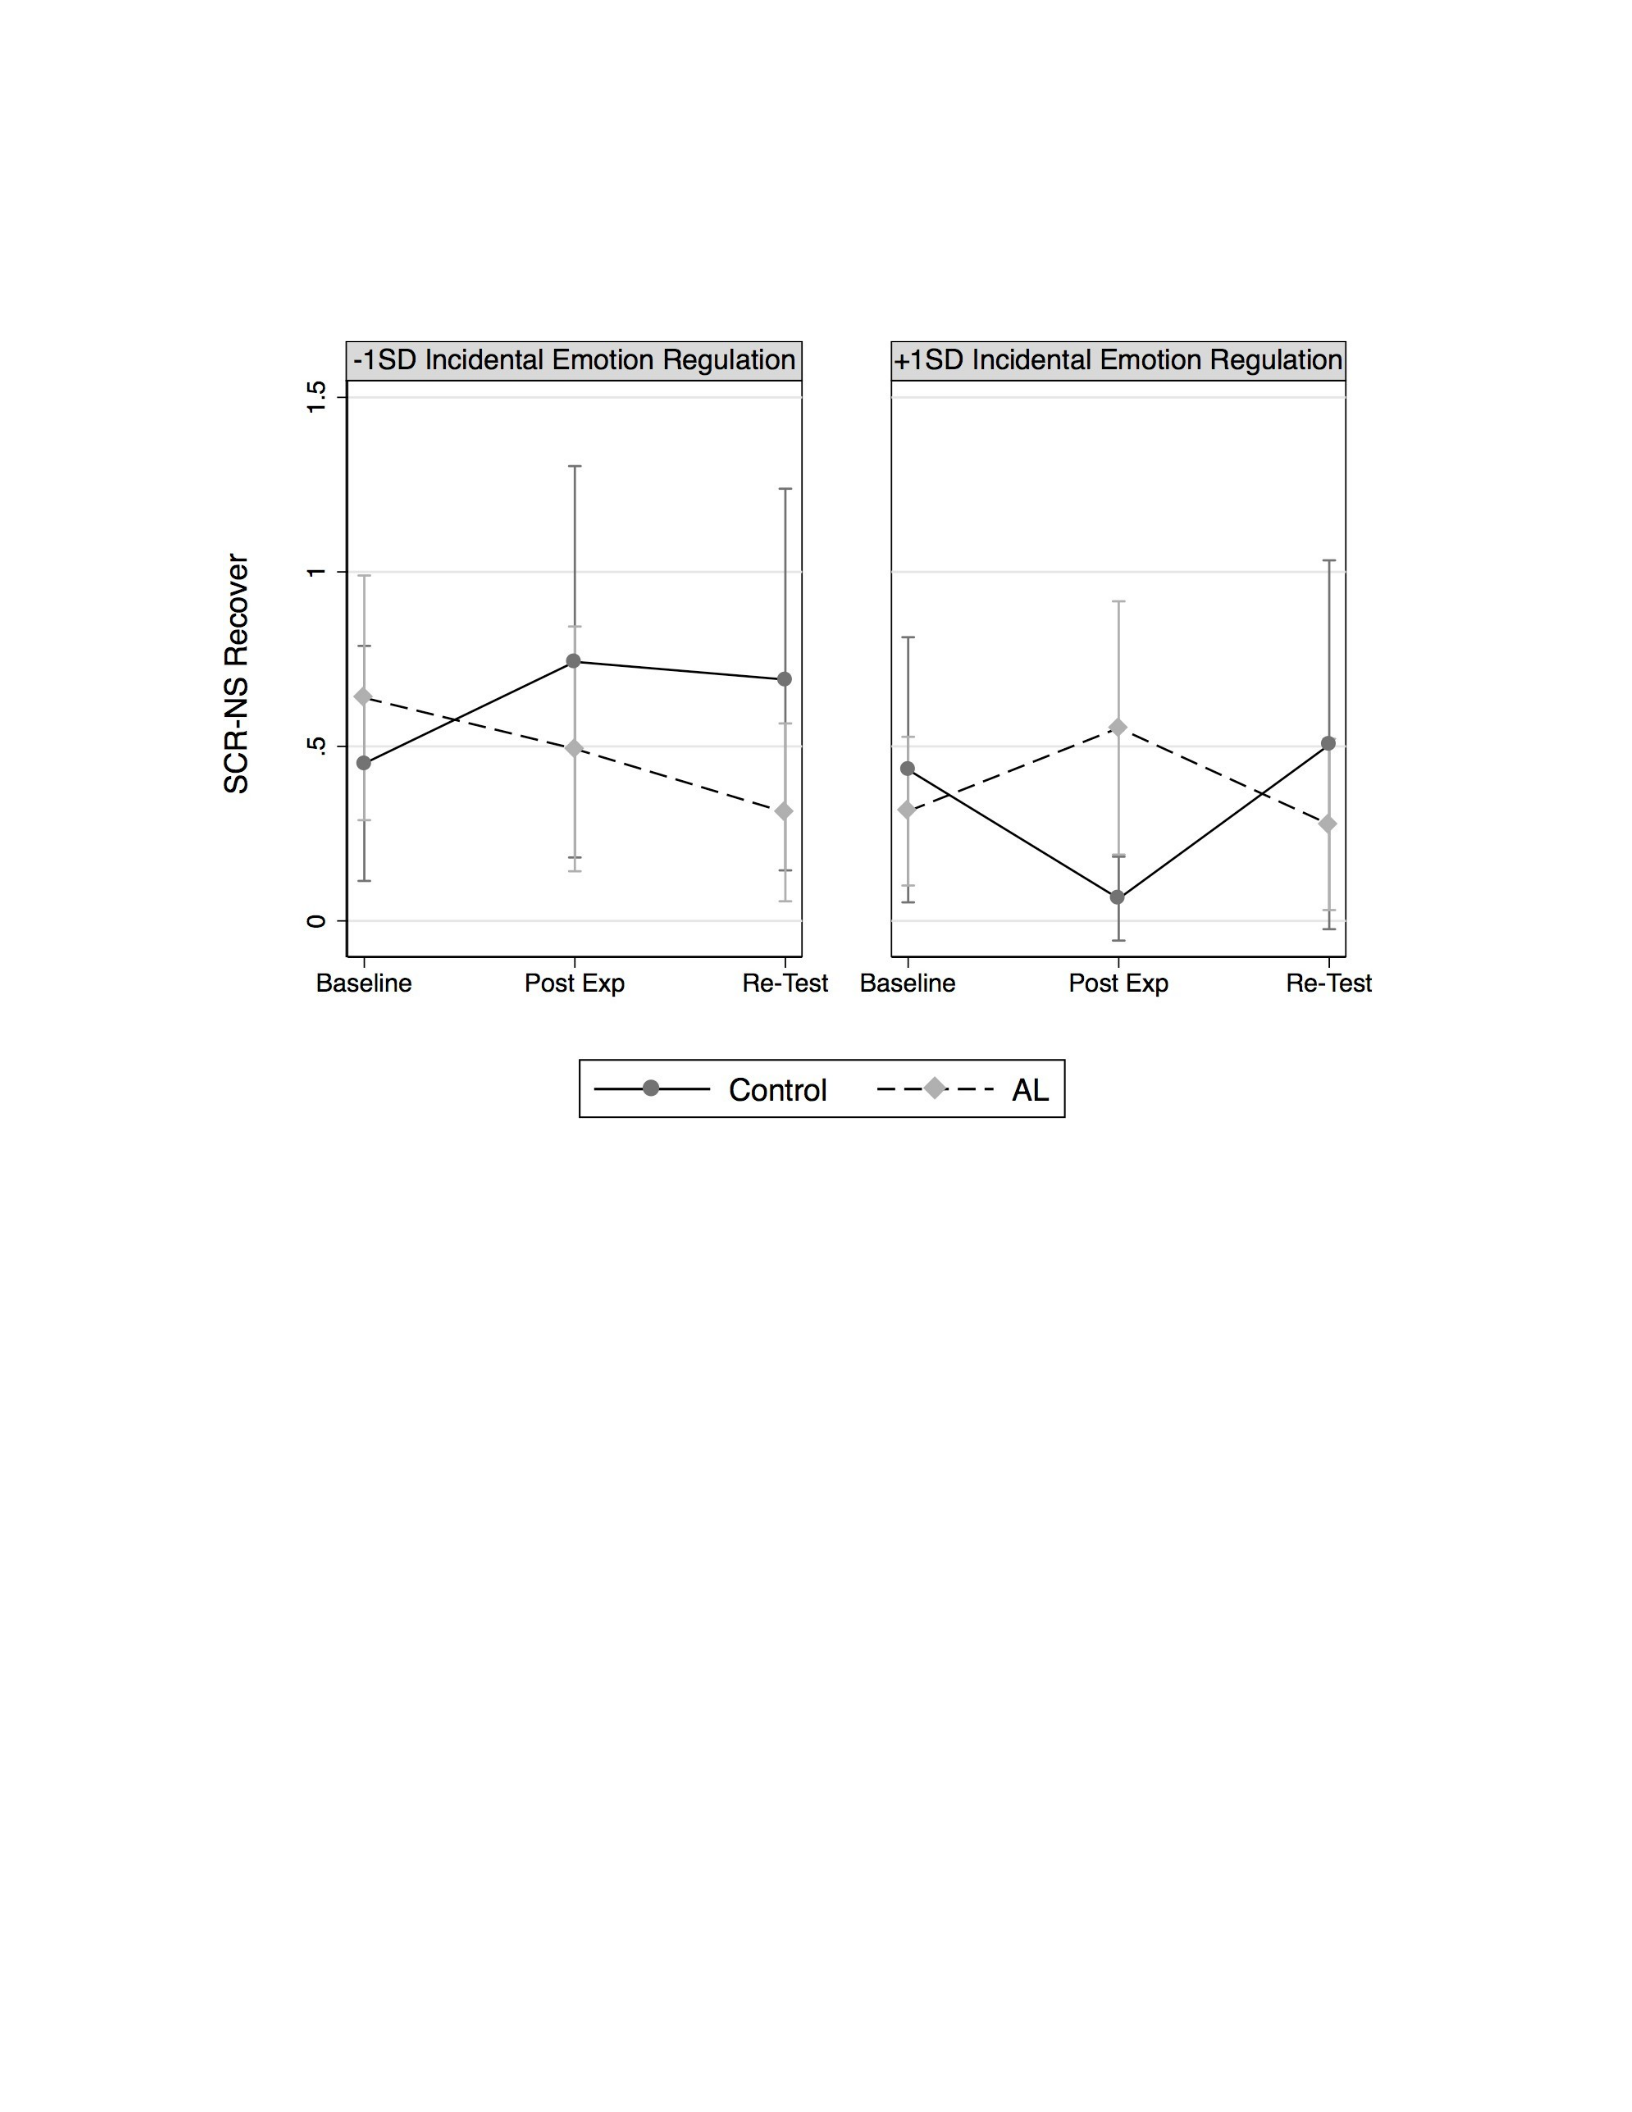
89
Figure 27. Moderation of Non-Specific Skin Conductance Response During Recovery Over
Time by Incidental Emotion Regulation and Group
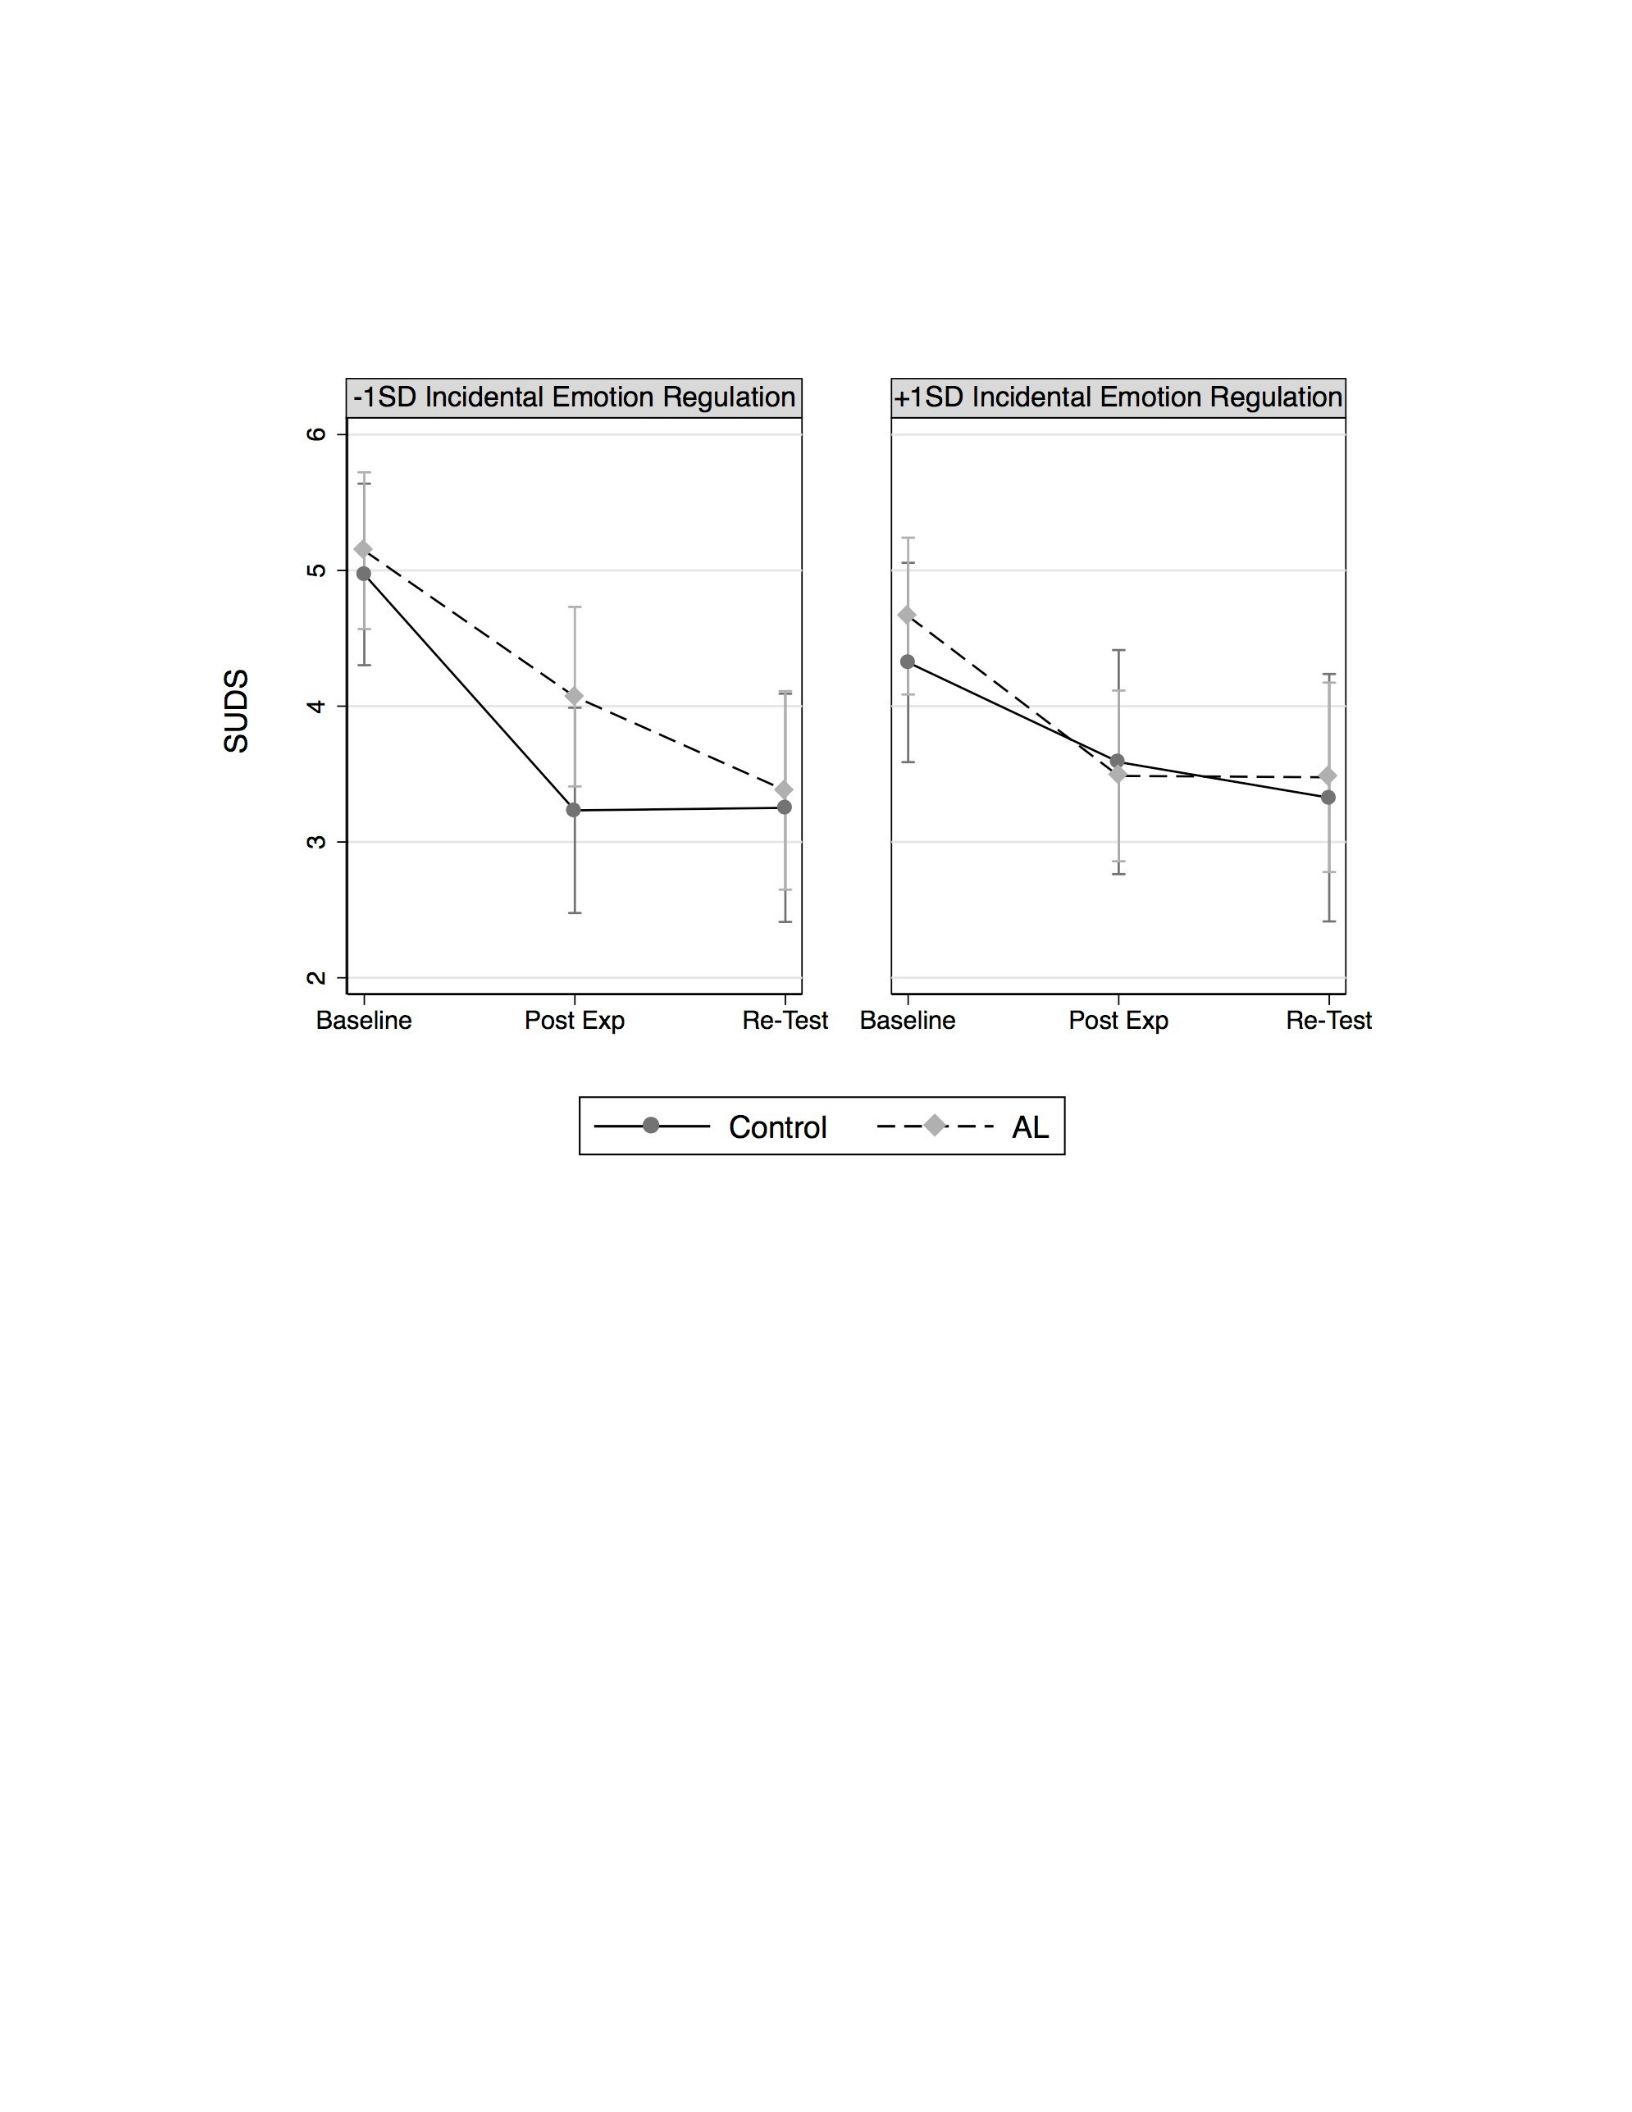
90
Figure 28. Moderation of Subjective Units of Distress Over Time by Incidental Emotion
Regulation and Group
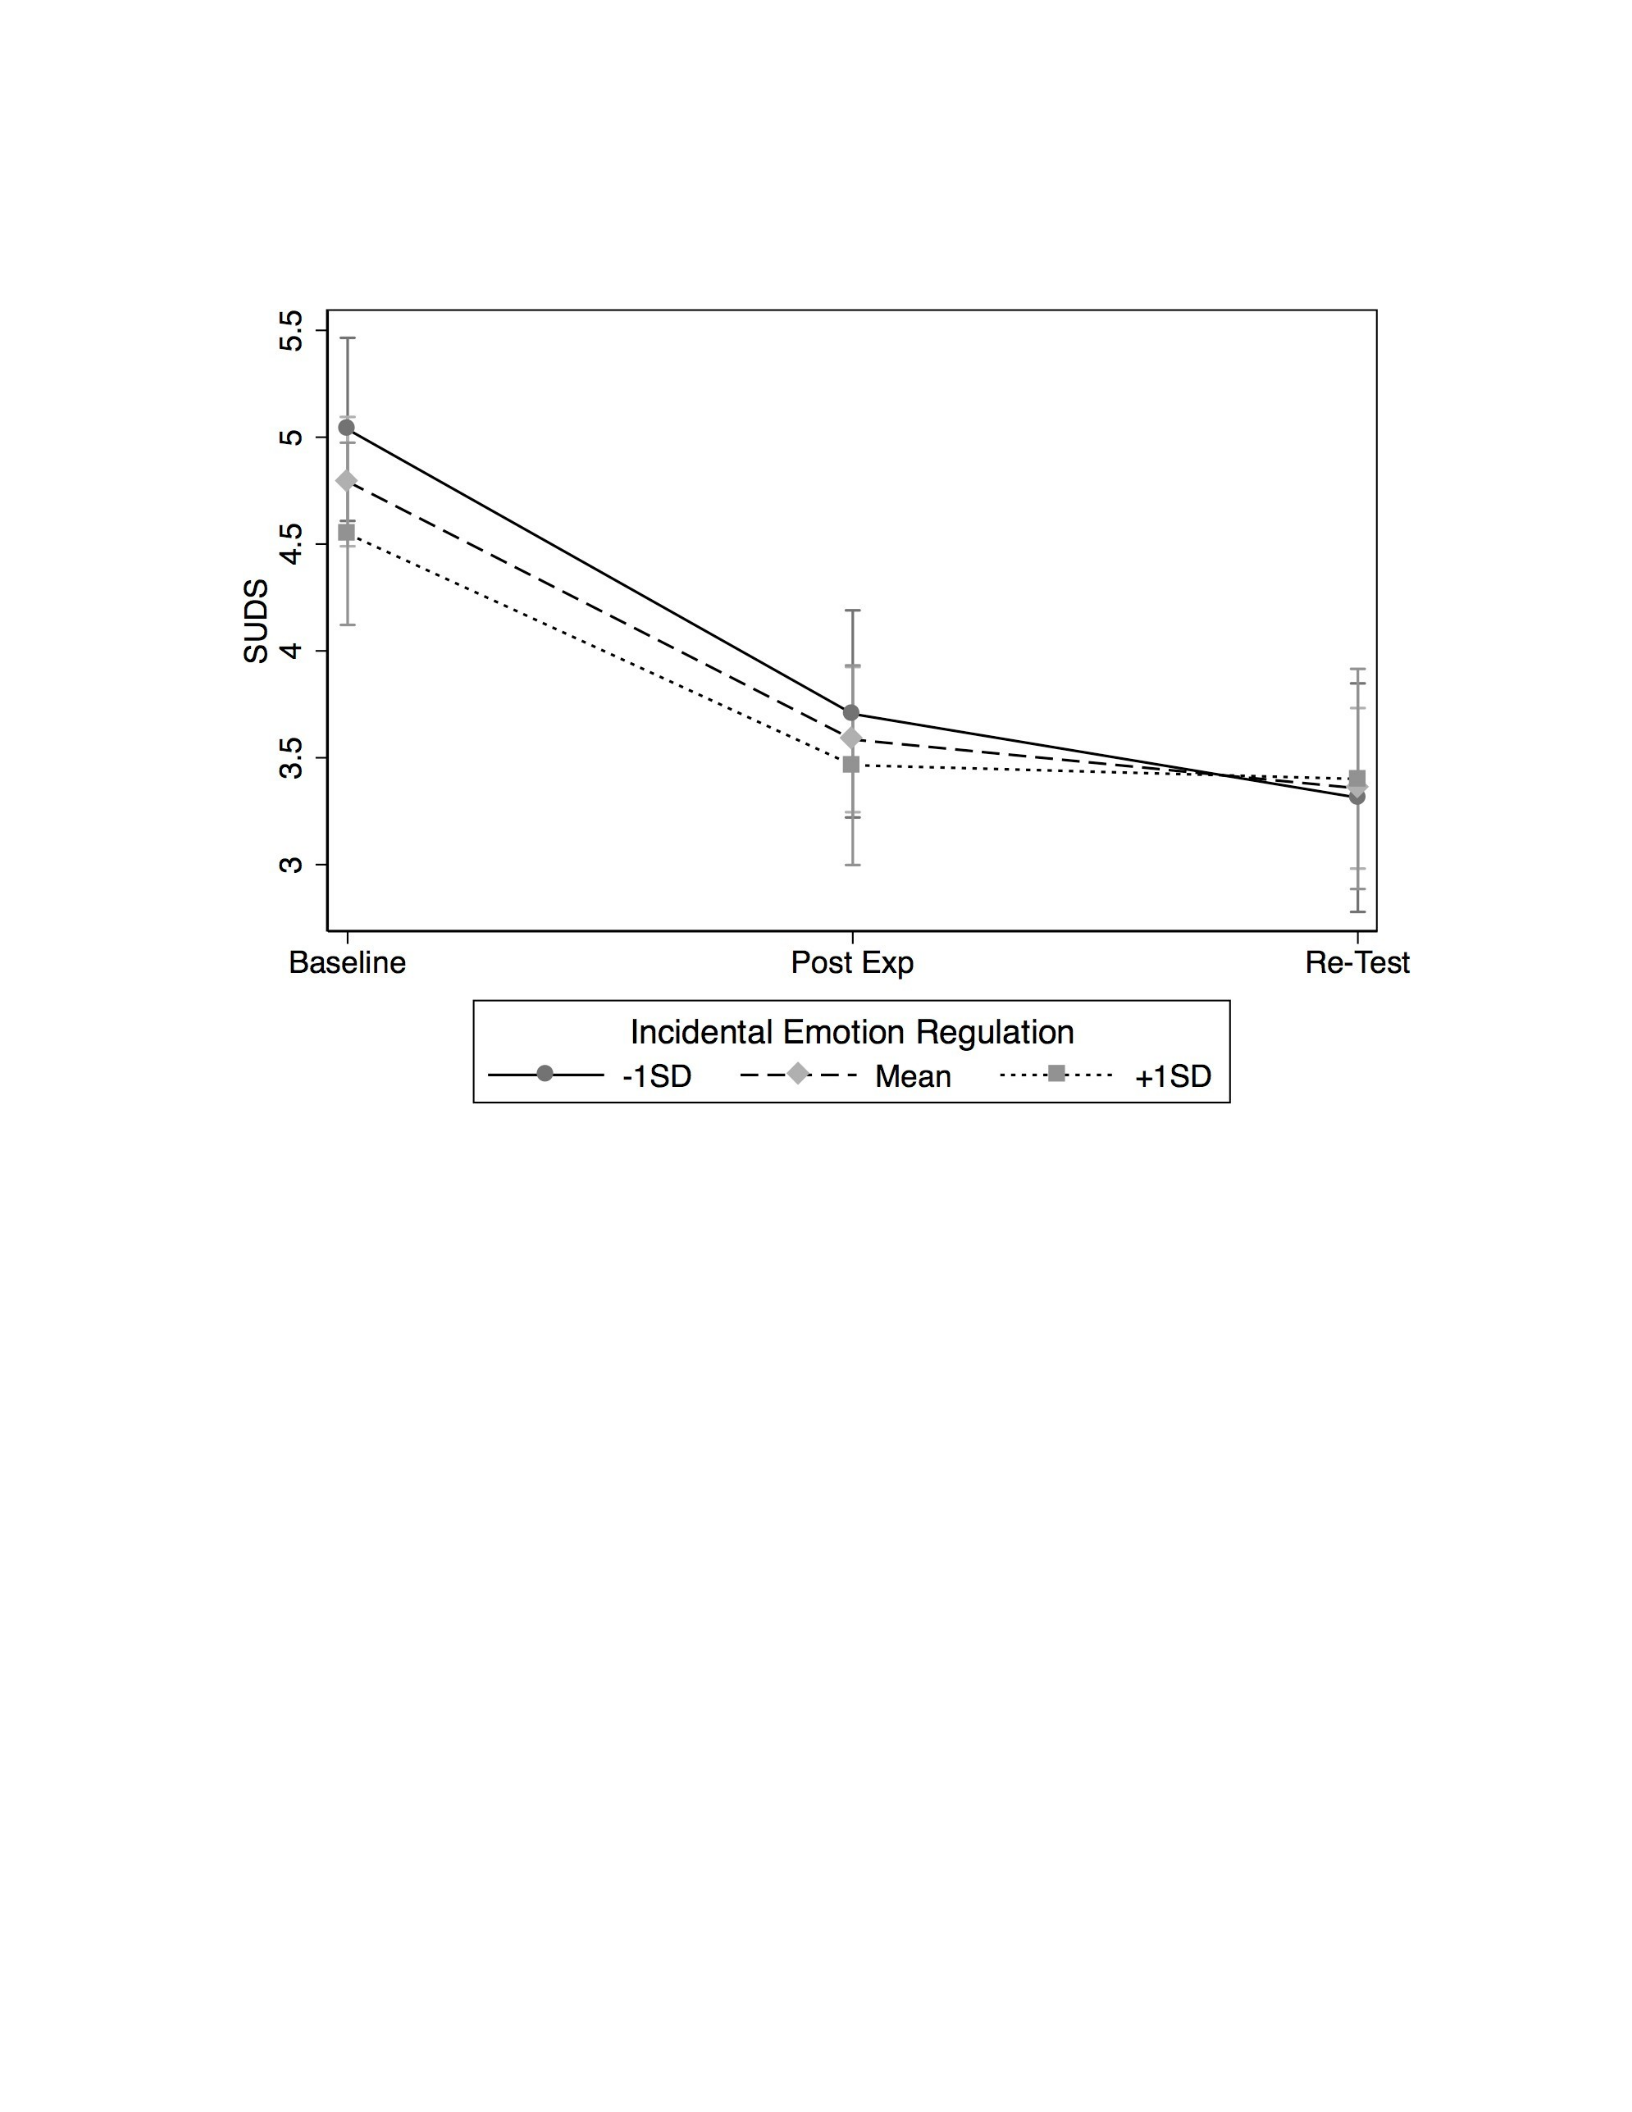
91
Figure 29. Prediction of Subjective Units of Distress Over Time by Incidental Emotion
Regulation
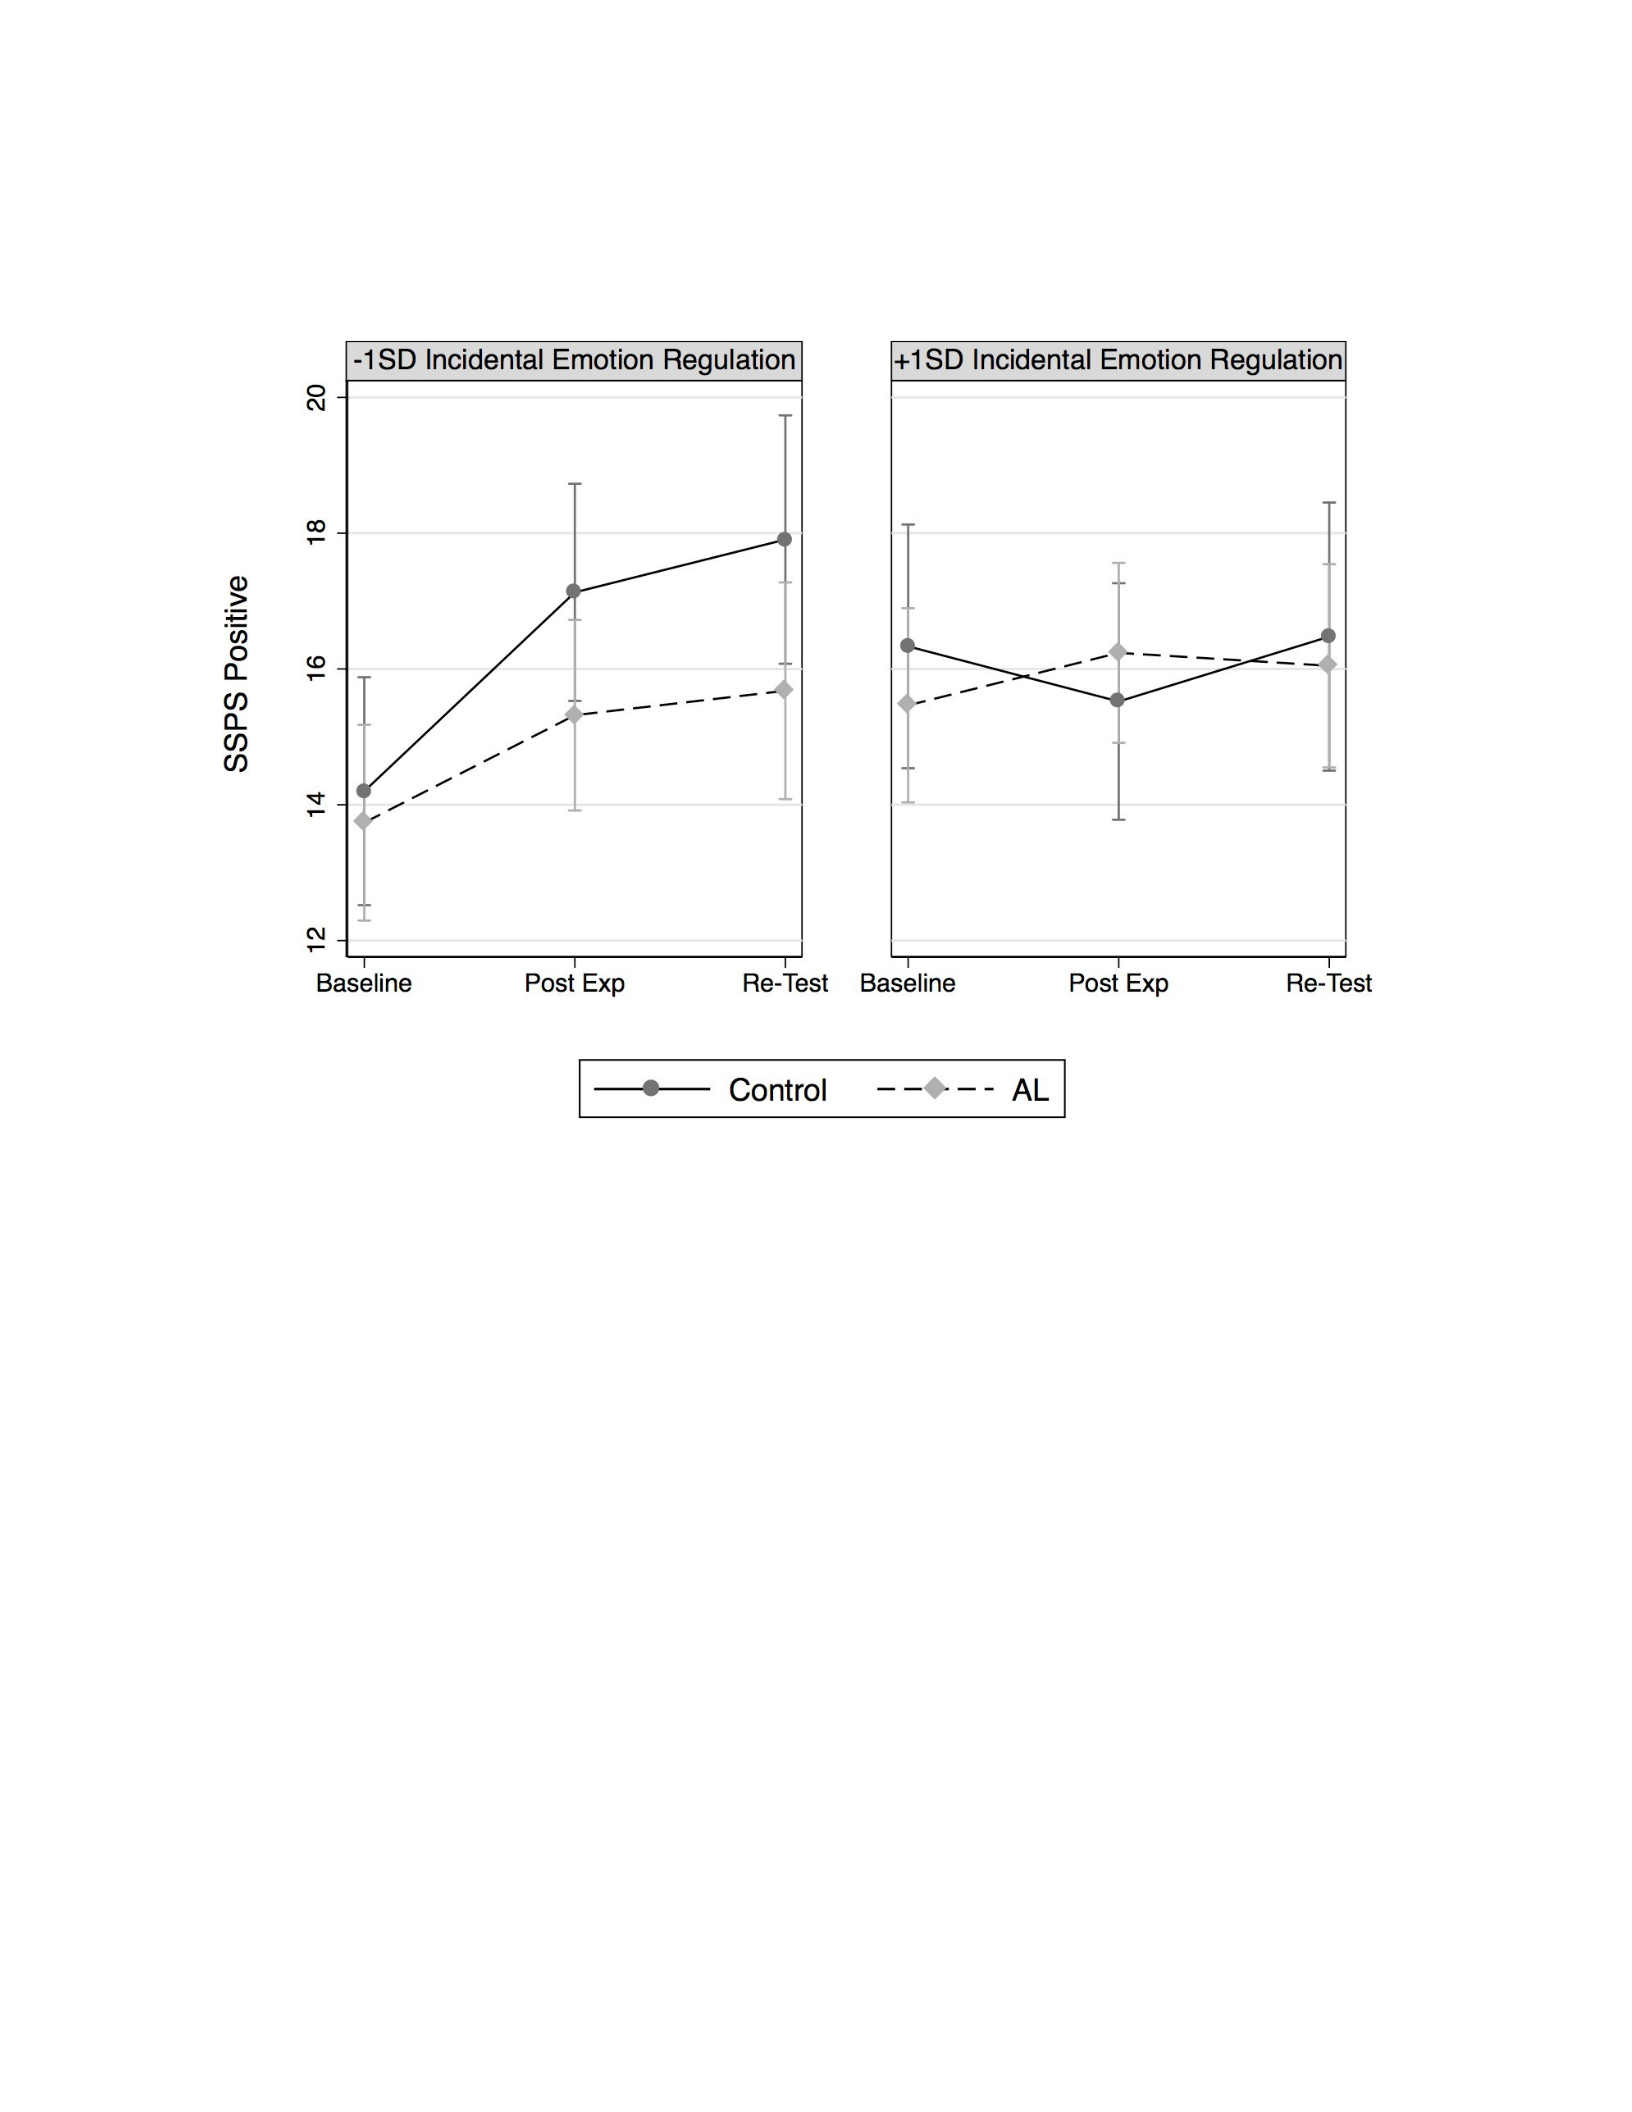
92
Figure 30. Moderation of Self Statements During Public Speaking Positive Over Time by
Incidental Emotion Regulation and Group
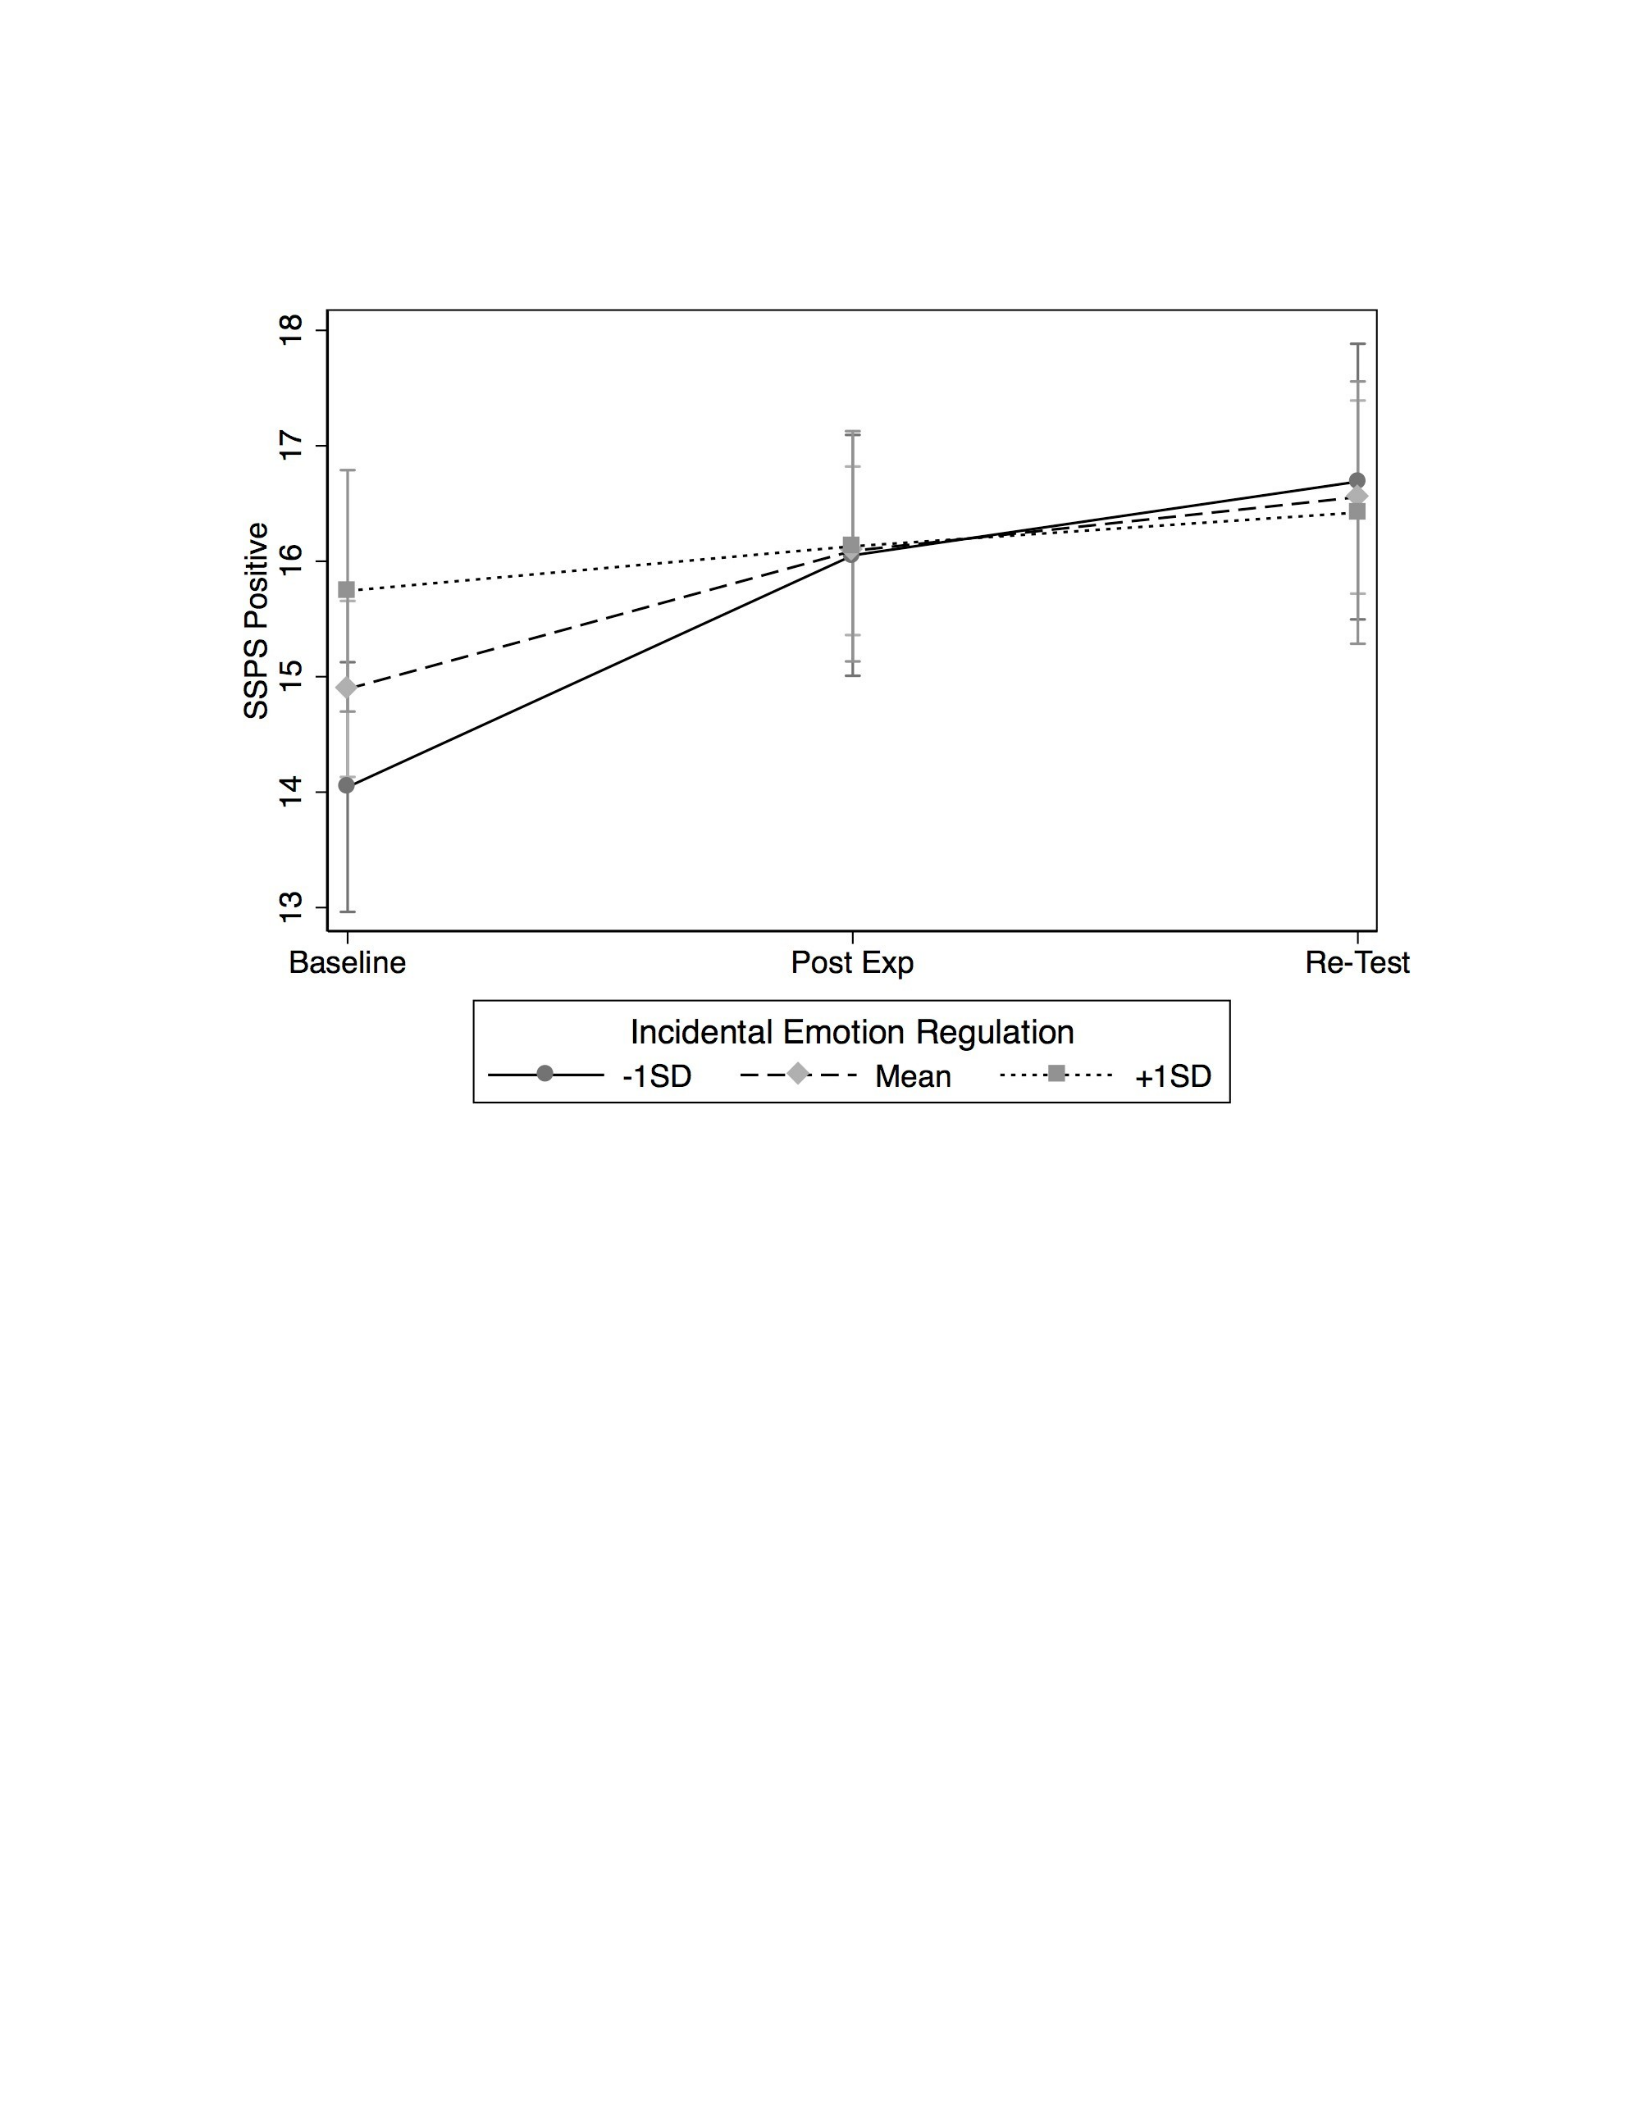
93
Figure 31. Prediction of Self Statements During Public Speaking Positive Over Time by
Incidental Emotion Regulation
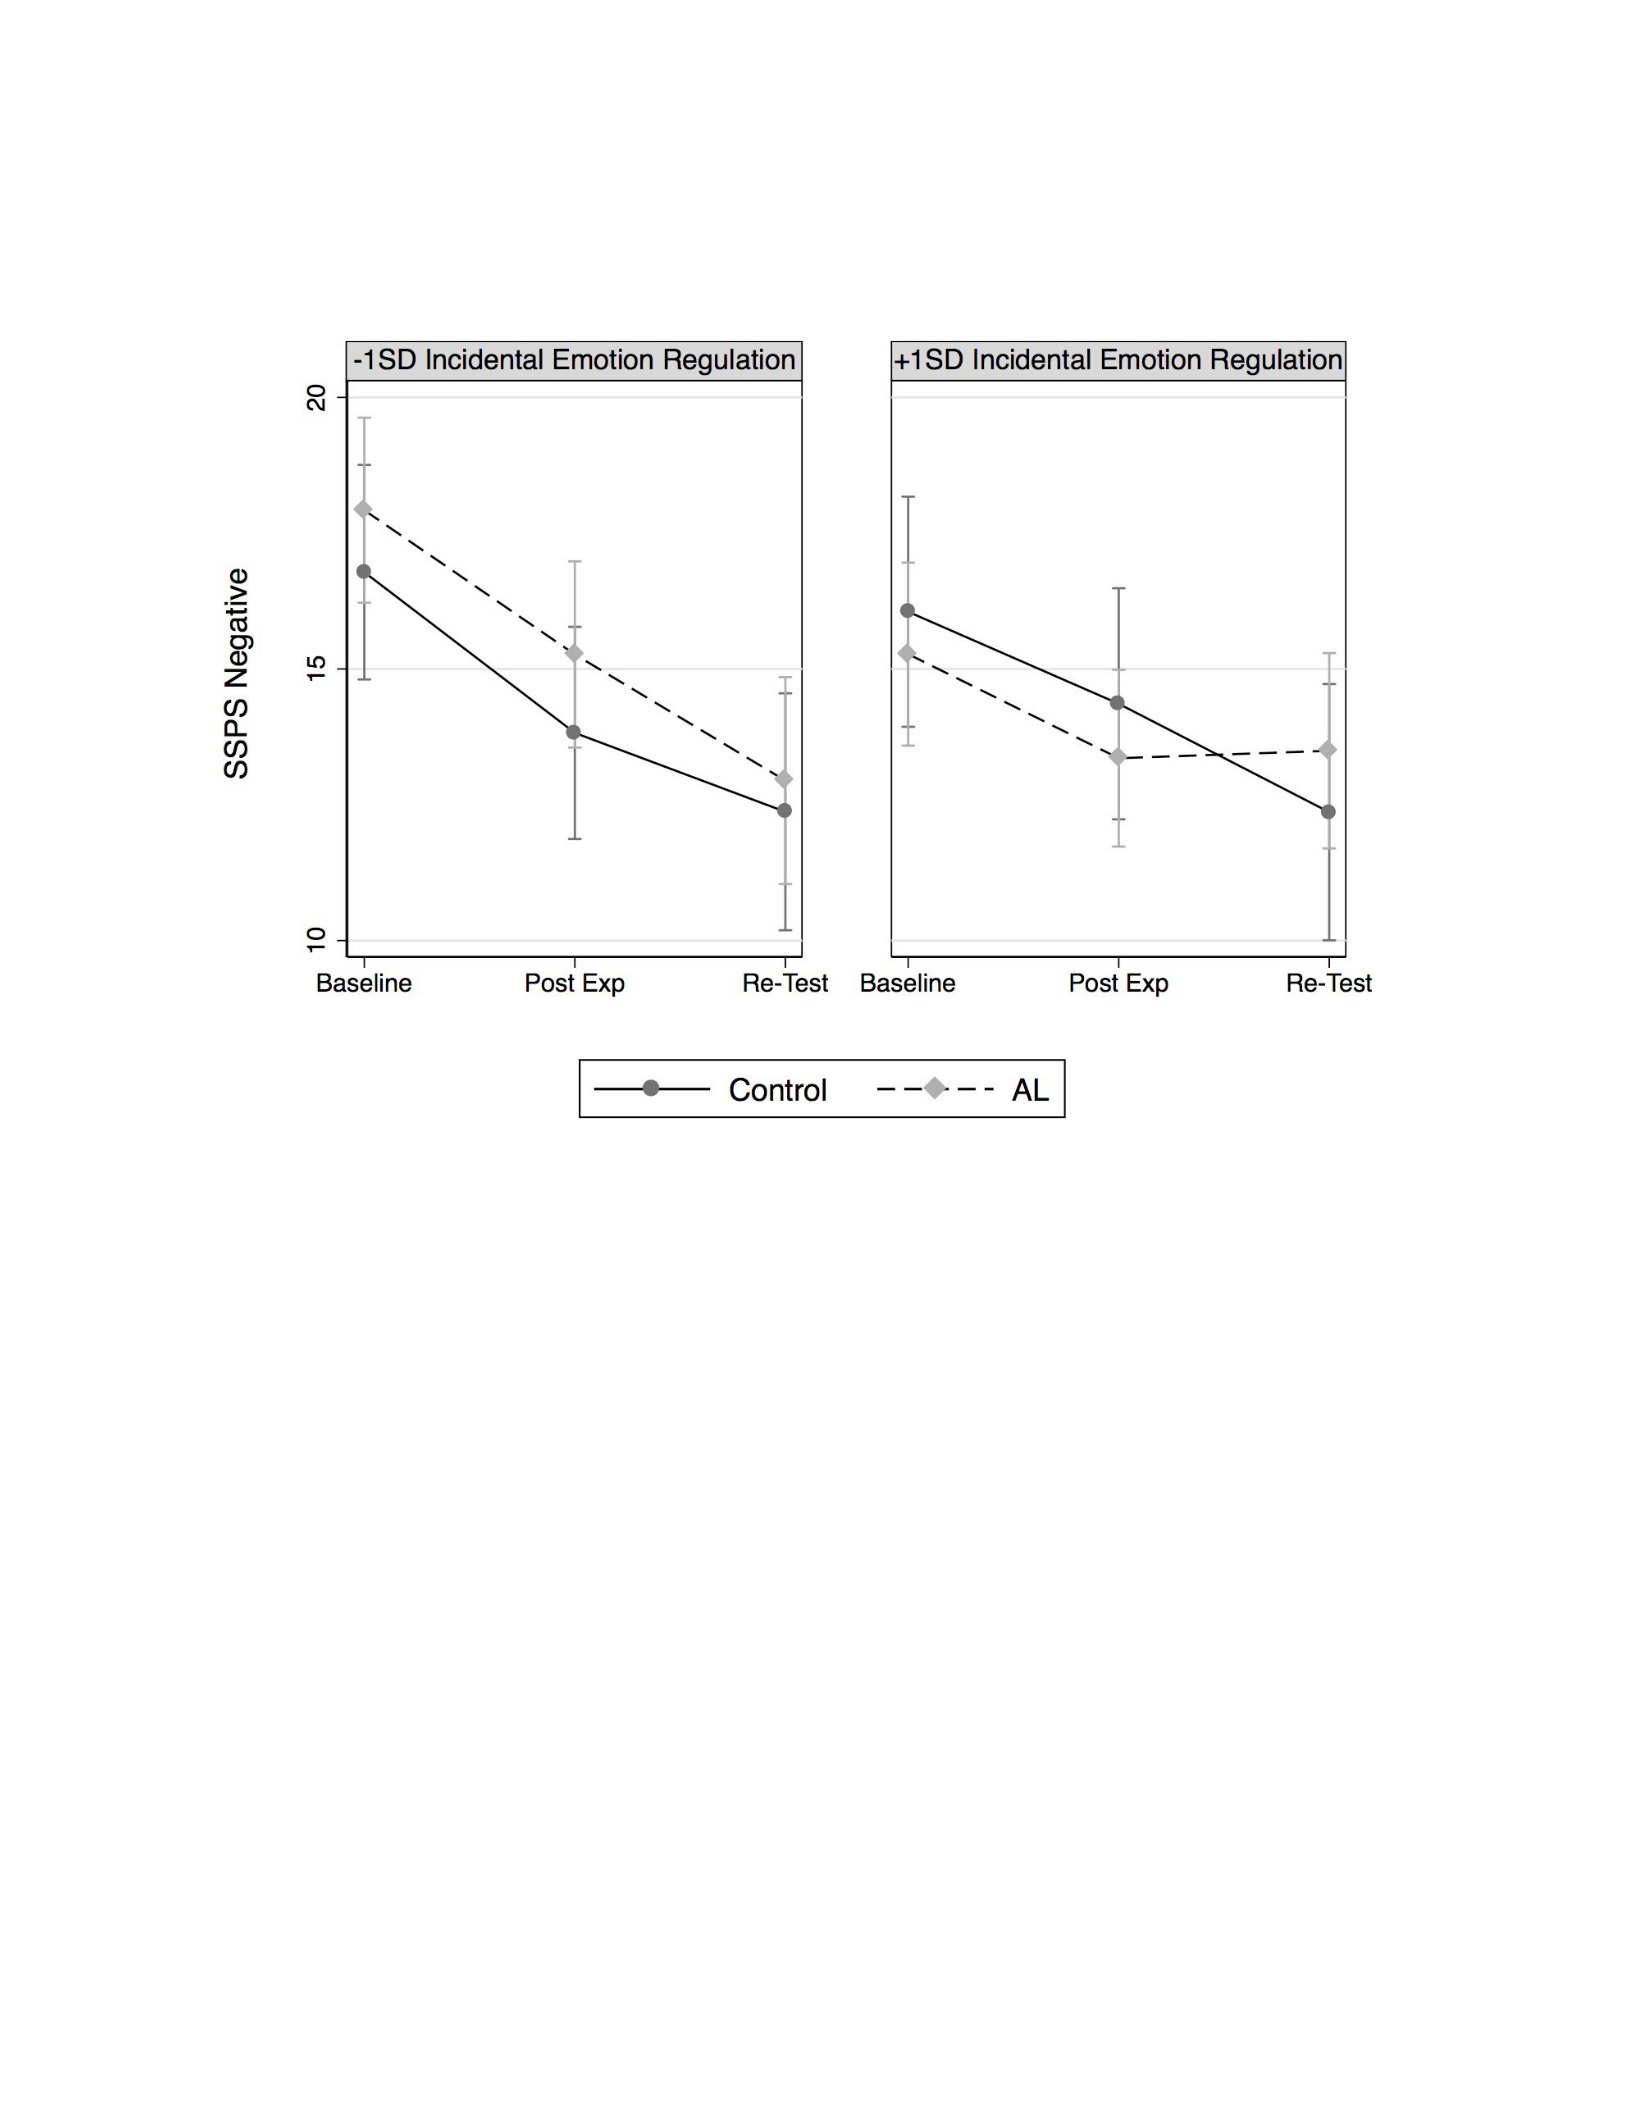
94
Figure 32. Moderation of Self Statements During Public Speaking Negative over Time by
Incidental Emotion Regulation and Group
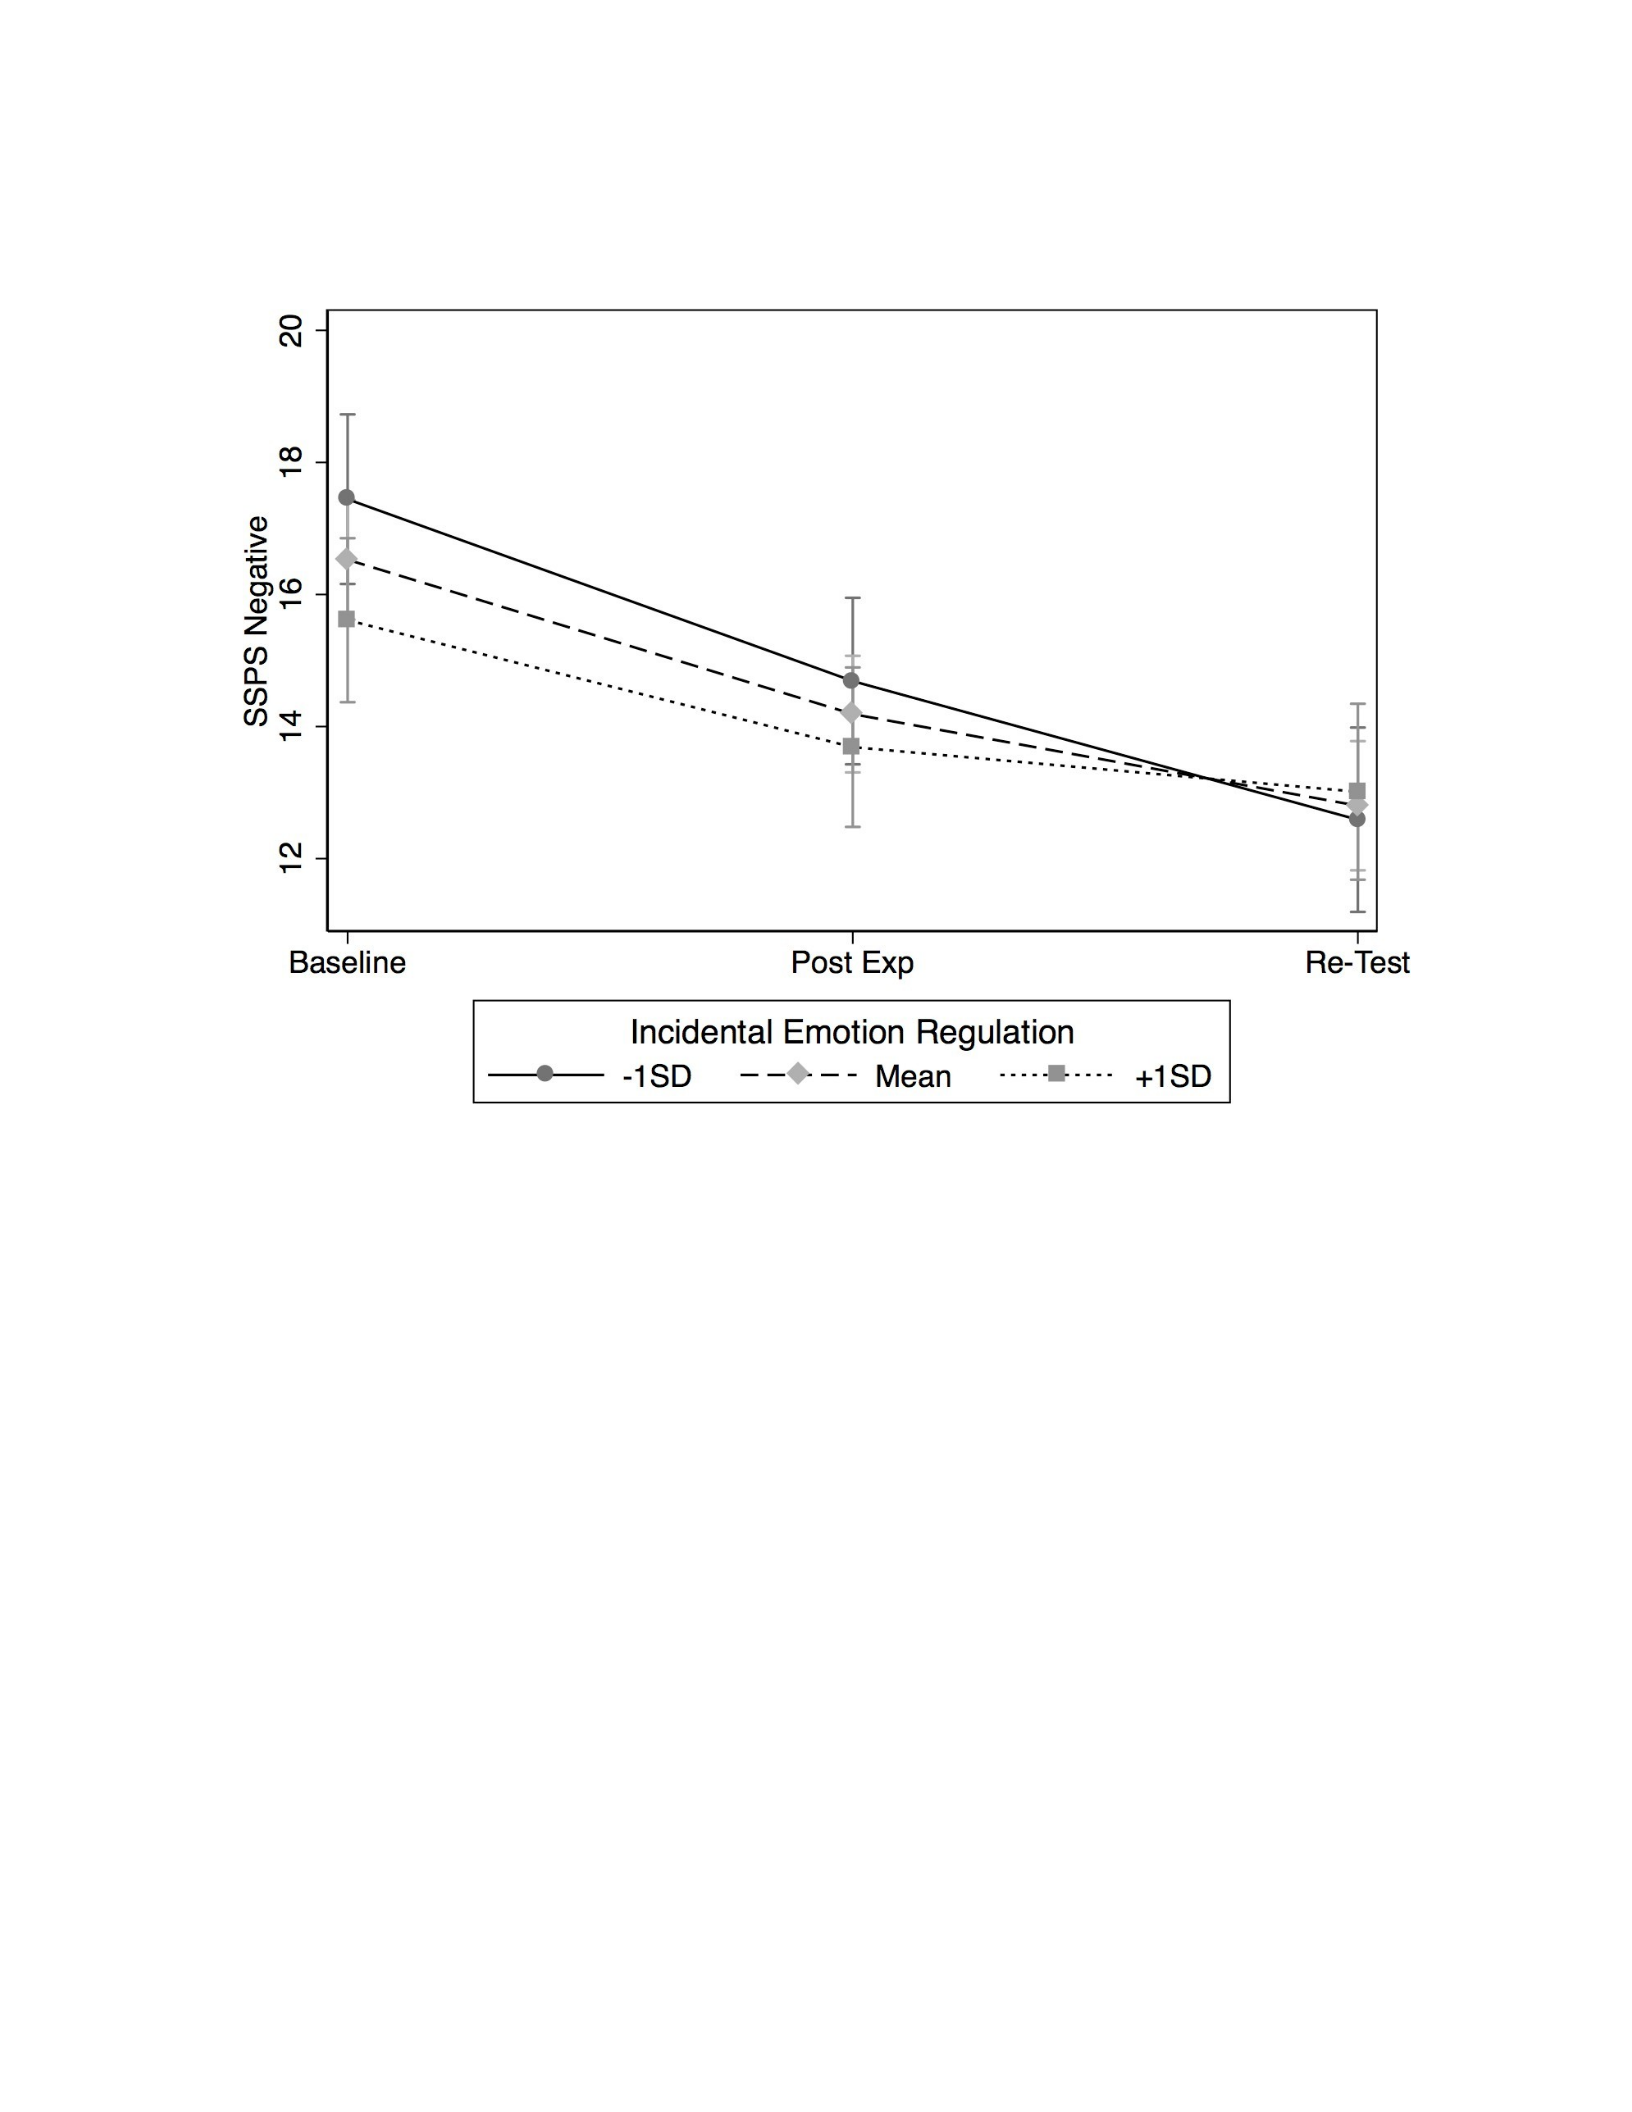
95
Figure 33. Prediction of Self Statements During Public Speaking Negative Over Time by
Incidental Emotion Regulation

96
References
Anderson, M. L. (2010). Neural reuse: A fundamental organizational principle of the brain.
Behavioral and Brain Sciences, 33(4), 245.
Arch, J. J., & Craske, M. G. (2008). Acceptance and commitment therapy and cognitive
behavioral therapy for anxiety disorders: Different treatments, similar mechanisms?
Clinical Psychology: Science and Practice, 15(4), 263–279.
Austenfeld, J. L., Paolo, A. M., & Stanton, A. L. (2006). Effects of writing about emotions
versus goals on psychological and physical health among third-year medical students.
Journal of Personality, 74(1), 267–286. doi:10.1111/j.1467-6494.2005.00375.x
Baumeister, R. F., & Leary, M. R. (1995). The need to belong: Desire for interpersonal
attachments as a fundamental human motivation. Psychological Bulletin, 117, 497–497.
Beatty, M. J., & Behnke, R. R. (1991). Effects of public speaking trait anxiety and intensity of
speaking task on heart rate during performance. Human Communication Research, 18(2),
147–176. doi:10.1111/j.1468-2958.1991.tb00542.x
Bouton, M. E. (1993). Context, time, and memory retrieval in the interference paradigms of
Pavlovian learning. Psychological Bulletin, 114(1), 80.
Bouton, M. E., Woods, A. M., Moody, E. W., Sunsay, C., & García-Gutiérrez, A. (2006).
Counteracting the context-dependence of extinction: Relapse and tests of some relapse
prevention methods. In M. G. Craske, D. Hermans, & D. Vansteenwegen (Eds.), Fear
and learning: From basic processes to clinical implications (pp. 175–196). Washington,
DC: American Psychological Association.

97
Bradley, M. M., Codispoti, M., Cuthbert, B. N., & Lang, P. J. (2001). Emotion and motivation I:
Defensive and appetitive reactions in picture processing. Emotion, 1(3), 276–298.
doi:10.1037/1528-3542.1.3.276
Braithwaite, J. J., Watson, D. G., Jones, R., & Rowe, M. (2013). A guide for analysing
electrodermal activity (EDA) and skin conductance responses (SCRs) for
psychophysiological experiments via the MP36R and AcqKnowledge software (No. 1).
University of Birmingham, UK: Selective Attention & Awareness Laboratory (SAAL),
Behavioral Brain Sciences Centre, School of Psychology.
Brühl, A. B., Rufer, M., Delsignore, A., Kaffenberger, T., Jäncke, L., & Herwig, U. (2011).
Neural correlates of altered general emotion processing in social anxiety disorder. Brain
Research, 1378, 72–83.
Burklund, L. J., Creswell, J. D., Irwin, M. R., & Lieberman, M. D. (2014). The common and
distinct neural bases of affect labeling and reappraisal in healthy adults. Frontiers in
Psychology, 5. doi:10.3389/fpsyg.2014.00221
Butler, A. C., Chapman, J. E., Forman, E. M., & Beck, A. T. (2006). The empirical status of
cognitive-behavioral therapy: A review of meta-analyses. Clinical Psychology Review,
26(1), 17–31. doi:10.1016/j.cpr.2005.07.003
Cacioppo, J. T., Tassinary, L. G., & Berntson, G. (2007). Handbook of Psychophysiology (3rd
ed.). New York, NY: Cambridge University Press.
Connor, K. M., Kobak, K. A., Churchill, L. E., Katzelnick, D., & Davidson, J. R. (2001). Mini-
SPIN: A brief screening assessment for generalized social anxiety disorder. Depression
and Anxiety, 14(2), 137–140.

98
Craske, M. G. (2003). Origins of phobias and anxiety disorders: Why more women than men?
Toronto, ON: Elsevier.
Craske, M. G., Antony, M. M., & Barlow, D. H. (2006). Mastering your fears and phobias:
Therapist guide. New York, NY: Oxford University Press.
Craske, M. G., Kircanski, K., Zelikowsky, M., Mystkowski, J., Chowdhury, N., & Baker, A.
(2008). Optimizing inhibitory learning during exposure therapy. Behaviour Research and
Therapy, 46(1), 5–27. doi:10.1016/j.brat.2007.10.003
Craske, M. G., Lang, A. J., Aikins, D., & Mystkowski, J. L. (2005). Cognitive behavioral
therapy for nocturnal panic. Behavior Therapy, 36(1), 43–54. doi:10.1016/S0005-
7894(05)80053-X
Craske, M. G., & Mystkowski, J. L. (2006). Exposure therapy and extinction: Clinical studies. In
M. G. Craske, D. Hermans, & D. Vansteenwegen (Eds.), Fear and learning: From basic
processes to clinical implications (pp. 217–233). Washington, DC: American
Psychological Association.
Craske, M. G., Niles, A. N., Burklund, L. J., Wolitzky-Taylor, K., Plumb, J., Saxbe, D., &
Lieberman, M. (In Press). Randomized controlled trial of cognitive behavioral therapy
and acceptance and commitment therapy for social anxiety disorder: Outcomes and
moderators. Journal of Consulting and Clinical Psychology.
Craske, M. G., Street, L. L., Jayaraman, J., & Barlow, D. H. (1991). Attention versus distraction
during in vivo exposure: Snake and spider phobias. Journal of Anxiety Disorders, 5(3),
199–211. doi:10.1016/0887-6185(91)90001-A
Deane, G. E. (1969). Cardiac activity during experimentally induced anxiety. Psychophysiology,
6(1), 17–30. doi:10.1111/j.1469-8986.1969.tb02879.x

99
Delgado, M. R., Nearing, K. I., LeDoux, J. E., & Phelps, E. A. (2008). Neural circuitry
underlying the regulation of conditioned fear and its relation to extinction. Neuron, 59(5),
829–838.
Dickerson, S. S., Gruenewald, T. L., & Kemeny, M. E. (2004). When the social self is
threatened: Shame, physiology, and health. Journal of Personality, 72(6), 1191–1216.
doi:10.1111/j.1467-6494.2004.00295.x
Dickerson, S. S., & Kemeny, M. E. (2004). Acute stressors and cortisol responses: A theoretical
integration and synthesis of laboratory research. Psychological Bulletin, 130(3), 355–391.
Eisenberger, N. I., & Lieberman, M. D. (2004). Why rejection hurts: a common neural alarm
system for physical and social pain. Trends in Cognitive Sciences, 8(7), 294–300.
Engebretson, T. O., Matthews, K. A., & Scheier, M. F. (1989). Relations between anger
expression and cardiovascular reactivity: Reconciling inconsistent findings through a
matching hypothesis. Journal of Personality and Social Psychology, 57(3), 513–21.
Feingold, A. (2009). Effect sizes for growth-modeling analysis for controlled clinical trials in the
same metric as for classical analysis. Psychological Methods, 14(1), 43–53.
doi:10.1037/a0014699
Feske, U., & Chambless, D. L. (1995). Cognitive behavioral versus exposure only treatment for
social phobia: A meta-analysis. Behavior Therapy, 26(4), 695–720. doi:10.1016/S0005-
7894(05)80040-1
Festinger, L. (1957). A Theory of Cognitive Dissonance. Stanford: Stanford University Press.
Frattaroli, J., Thomas, M., & Lyubomirsky, S. (2011). Opening up in the classroom: Effects of
expressive writing on graduate school entrance exam performance. Emotion, 11(3), 691.

100
Gorno-Tempini, M. L., Pradelli, S., Serafini, M., Pagnoni, G., Baraldi, P., Porro, C., … Nichelli,
P. (2001). Explicit and incidental facial expression processing: An fMRI study.
NeuroImage, 14(2), 465–473. doi:10.1006/nimg.2001.0811
Hahn, A., Stein, P., Windischberger, C., Weissenbacher, A., Spindelegger, C., Moser, E., …
Lanzenberger, R. (2011). Reduced resting-state functional connectivity between
amygdala and orbitofrontal cortex in social anxiety disorder. NeuroImage, 56(3), 881–
889. doi:10.1016/j.neuroimage.2011.02.064
Hariri, A. R., Bookheimer, S. Y., & Mazziotta, J. C. (2000). Modulating emotional responses:
Effects of a neocortical network on the limbic system. Neuroreport, 11(1), 43–48.
Hariri, A. R., Mattay, V. S., Tessitore, A., Fera, F., & Weinberger, D. R. (2003). Neocortical
modulation of the amygdala response to fearful stimuli. Biological Psychiatry, 53(6),
494–501.
Hartley, C. A., Fischl, B., & Phelps, E. A. (2011). Brain Structure correlates of individual
differences in the acquisition and inhibition of conditioned fear. Cerebral Cortex, 21(9),
1954–1962. doi:10.1093/cercor/bhq253
Hayes, S. C., Strosahl, K. D., & Wilson, K. G. (1999). Acceptance and commitment therapy: An
experiential approach to behavior change. New York, NY: The Guilford Press.
Heimberg, R. G. (2002). Cognitive-behavioral therapy for social anxiety disorder: Current status
and future directions. Biological Psychiatry, 51(1), 101–108.
Hemenover, S. H. (2003). The good, the bad, and the healthy: Impacts of emotional disclosure of
trauma on resilient self-concept and psychological distress. Personality and Social
Psychology Bulletin, 29(10), 1236–1244.

101
Hofmann, S. G., & DiBartolo, P. M. (2000). An instrument to assess self-statements during
public speaking: Scale development and preliminary psychometric properties. Behavior
Therapy, 31(3), 499–515.
Hofmann, S. G., & Smits, J. A. J. (2008). Cognitive-behavioral therapy for adult anxiety
disorders: A meta-analysis of randomized placebo-controlled trials. The Journal of
Clinical Psychiatry, 69(4), 621–632.
Hope, D. A., Heimberg, R. G., Juster, H. A., & Turk, C. L. (2000). Managing social anxiety: A
cognitive-behavioral therapy approach client workbook. New York, NY: Oxford
University Press.
Hugdahl, K. (1995). Psychophysiology: The mind-body perspective. Boston, MA: Harvard
University Press.
Kandel, E. R., & Schwartz, J. H. (1982). Molecular biology of learning: Modulation of
transmitter release. Science, 218(4571), 433–443.
Kim, M. J., Loucks, R. A., Palmer, A. L., Brown, A. C., Solomon, K. M., Marchante, A. N., &
Whalen, P. J. (2011). The structural and functional connectivity of the amygdala: From
normal emotion to pathological anxiety. Behavioural Brain Research, 223(2), 403–410.
doi:10.1016/j.bbr.2011.04.025
Kircanski, K., Lieberman, M. D., & Craske, M. G. (2012). Feelings into words: Contributions of
language to exposure therapy. Psychological Science. doi:10.1177/0956797612443830
Klein, K., & Boals, A. (2001). Expressive writing can increase working memory capacity.
Journal of Experimental Psychology: General, 130(3), 520.

102
Knight, D. C., Smith, C. N., Cheng, D. T., Stein, E. A., & Helmstetter, F. J. (2004). Amygdala
and hippocampal activity during acquisition and extinction of human fear conditioning.
Cognitive, Affective, & Behavioral Neuroscience, 4(3), 317–325.
Lang, P. J., Bradley, M. M., & Cuthbert, B. N. (1999). International affective picture system
(IAPS): Technical manual and affective ratings. Gainesville, FL: The Center for
Research in Psychophysiology, University of Florida.
Lecrubier, Y., Sheehan, D., Weiller, E., Amorim, P., Bonora, I., Harnett Sheehan, K., … Dunbar,
G. (1997). The Mini International Neuropsychiatric Interview (MINI). A short diagnostic
structured interview: reliability and validity according to the CIDI. European Psychiatry,
12(5), 224–231. doi:10.1016/S0924-9338(97)83296-8
LeDoux, J. E. (2000). Emotion circuits in the brain. Annual Review of Neuroscience, 23(1), 155–
184.
Lepore, S. J., Silver, R. C., Wortman, C. B., & Wayment, H. A. (1996). Social constraints,
intrusive thoughts, and depressive symptoms among bereaved mothers. Journal of
Personality and Social Psychology, 70(2), 271.
Levin, A. P., Saoud, J. B., Strauman, T., Gorman, J. M., Fyer, A. J., Crawford, R., & Liebowitz,
M. R. (1993). Responses of “generalized” and “discrete” social phobics during public
speaking. Journal of Anxiety Disorders, 7(3), 207–221. doi:10.1016/0887-
6185(93)90003-4
Lieberman, M. D. (2003). Reflexive and reflective judgment processes: A social cognitive
neuroscience approach. In J. P. Forgas, K. D. Williams, & W. von (Eds.), Social
judgments: Implicit and explicit processes (pp. 44–67). New York, NY: Cambridge
University Press.

103
Lieberman, M. D. (2011). Why symbolic processing of affect can disrupt negative affect: Social
cognitive and affective neuroscience investigations. Social Neuroscience: Toward
Understanding the Underpinnings of the Social Mind, 188–209.
Lieberman, M. D., Eisenberger, N. I., Crockett, M. J., Tom, S. M., Pfeifer, J. H., & Way, B. M.
(2007). Putting feelings into words: Affect labeling disrupts amygdala activity in
response to affective stimuli. Psychological Science, 18(5), 421–428.
doi:10.1111/j.1467- 9280.2007.01916.x
Lieberman, M. D., Inagaki, T. K., Tabibnia, G., & Crockett, M. J. (2011). Subjective responses
to emotional stimuli during labeling, reappraisal, and distraction. Emotion, 11(3), 468–
480. doi:10.1037/a0023503
Loerinc, A., Meuret, A., Twohig, M., Rosenfield, D., & Craske, M. G. (Submitted for
Publication). Response rates in CBT for anxiety disorders: Measurement matters.
Löwe, B., Kroenke, K., Herzog, W., & Gräfe, K. (2004). Measuring depression outcome with a
brief self-report instrument: Sensitivity to change of the Patient Health Questionnaire
(PHQ-9). Journal of Affective Disorders, 81(1), 61–66. doi:10.1016/S0165-
0327(03)00198-8
Löwe, B., Spitzer, R. L., Gräfe, K., Kroenke, K., Quenter, A., Zipfel, S., … Herzog, W. (2004).
Comparative validity of three screening questionnaires for DSM-IV depressive disorders
and physicians’ diagnoses. Journal of Affective Disorders, 78(2), 131–140.
Lu, Q., & Stanton, A. L. (2009). How benefits of expressive writing vary as a function of writing
instructions, ethnicity and ambivalence over emotional expression. Psychology & Health,
25(6), 669–684. doi:10.1080/08870440902883196

104
Masterson, F. A., & Crawford, M. (2010). The defense motivation system: A theory of
avoidance behavior. Behavioral and Brain Sciences, 5(04), 661.
doi:10.1017/S0140525X00014114
McCroskey, J. C. (1970). Measures of communication‐bound anxiety. Speech Monographs,
37(4), 269–277. doi:10.1080/03637757009375677
Milad, M. R., Quinn, B. T., Pitman, R. K., Orr, S. P., Fischl, B., & Rauch, S. L. (2005).
Thickness of ventromedial prefrontal cortex in humans is correlated with extinction
memory. Proceedings of the National Academy of Sciences of the United States of
America, 102(30), 10706–10711.
Milad, M. R., & Quirk, G. J. (2002). Neurons in medial prefrontal cortex signal memory for fear
extinction. Nature, 420(6911), 70–74. doi:10.1038/nature01138
Mineka, S., Mystkowski, J. L., Hladek, D., & Rodriguez, B. I. (1999). The effects of changing
contexts on return of fear following exposure therapy for spider fear. Journal of
Consulting and Clinical Psychology, 67(4), 599.
Myers, R. M. (1974). Validation of systematic desensitization of speech anxiety through galvanic
skin response. Speech Monographs, 41(3), 233–235. doi:10.1080/03637757409375841
Narumoto, J., Yamada, H., Iidaka, T., Sadato, N., Fukui, K., Itoh, H., & Yonekura, Y. (2000).
Brain regions involved in verbal or non-verbal aspects of facial emotion recognition.
Neuroreport, 11(11), 2571–2576.
Niles, A. N., Haltom, K. E. B., Mulvenna, C. M., Lieberman, M. D., & Stanton, A. L. (2014).
Randomized controlled trial of expressive writing for psychological and physical health:
The moderating role of emotional expressivity. Anxiety, Stress, and Coping, 27(1), 1–17.
doi:10.1080/10615806.2013.802308

105
Niles, A. N., Mesri, B., Burklund, L. J., Lieberman, M. D., & Craske, M. G. (2013). Attentional
bias and emotional reactivity as predictors and moderators of behavioral treatment for
social phobia. Behaviour Research and Therapy, 51(10), 669–679.
doi:10.1016/j.brat.2013.06.005
Novalis, P. N., M. D., Rojcewicz, S. J., M. D., & Peele, R., M. D. (1993). Clinical manual of
supportive psychotherapy. Washington, DC: American Psychiatric Press.
Öhman, A., & Mineka, S. (2001). Fears, phobias, and preparedness: Toward an evolved module
of fear and fear learning. Psychological Review, 108(3), 483.
Páez, D., Velasco, C., & González, J. L. (1999). Expressive writing and the role of alexythimia
as a dispositional deficit in self-disclosure and psychological health. Journal of
Personality and Social Psychology, 77(3), 630–641.
Pennebaker, J. W. (1997). Writing about emotional experiences as a therapeutic process.
Psychological Science, 8(3), 162–166.
Pennebaker, J. W., & Beall, S. K. (1986). Confronting a traumatic event: Toward an
understanding of inhibition and disease. Journal of Abnormal Psychology, 95(3), 274–
281.
Phelps, E. A., Delgado, M. R., Nearing, K. I., & LeDoux, J. E. (2004). Extinction learning in
humans: Role of the amygdala and vmPFC. Neuron, 43(6), 897–905.
doi:10.1016/j.neuron.2004.08.042
Pollard, C. A., & Henderson, J. G. (1988). Four types of social phobia in a community sample.
The Journal of Nervous and Mental Disease, 176(7), 440–445.
Rachman, S., Grüter-Andrew, J., & Shafran, R. (2000). Post-event processing in social anxiety.
Behaviour Research and Therapy, 38(6), 611–617. doi:10.1016/S0005-7967(99)00089-3

106
Ramirez, G., & Beilock, S. L. (2011). Writing about testing worries boosts exam performance in
the classroom. Science, 331(6014), 211.
Rapee, R. M., & Heimberg, R. G. (1997). A cognitive-behavioral model of anxiety in social
phobia. Behaviour Research and Therapy, 35(8), 741–756.
Rapee, R. M., & Lim, L. (1992). Discrepancy between self-and observer ratings of performance
in social phobics. Journal of Abnormal Psychology, 101(4), 728.
Rescorla, R. A., & Heth, C. D. (1975). Reinstatement of fear to an extinguished conditioned
stimulus. Journal of Experimental Psychology: Animal Behavior Processes, 1(1), 88.
Resick, P. A., & Schnicke, M. (1993). Cognitive processing therapy for rape victims: A
treatment manual (Vol. 4). Newbury Park, CA: Sage Publications.
Ricker, S., & Bouton, M. (1996). Reacquisition following extinction in appetitive conditioning.
Learning & Behavior, 24(4), 423–436. doi:10.3758/BF03199014
Rodebaugh, T. L., Holaway, R. M., & Heimberg, R. G. (2004). The treatment of social anxiety
disorder. Clinical Psychology Review, 24(7), 883–908. doi:10.1016/j.cpr.2004.07.007
Rowe, M. K., & Craske, M. G. (1998). Effects of varied-stimulus exposure training on fear
reduction and return of fear. Behaviour Research and Therapy, 36(7-8), 719–734.
Selya, A. S., Rose, J. S., Dierker, L. C., Hedeker, D., & Mermelstein, R. J. (2012). A practical
guide to calculating cohen’s f(2), a measure of local effect size, from PROC MIXED.
Frontiers in Psychology, 3, 111. doi:10.3389/fpsyg.2012.00111
Shah, S. G., Klumpp, H., Angstadt, M., Nathan, P. J., & Phan, K. L. (2009). Amygdala and
insula response to emotional images in patients with generalized social anxiety disorder.
Journal of Psychiatry and Neuroscience, 34(4), 296–302.

107
Smyth, J. M., Hockemeyer, J. R., & Tulloch, H. (2008). Expressive writing and post-traumatic
stress disorder: Effects on trauma symptoms, mood states, and cortisol reactivity. British
Journal of Health Psychology, 13(1), 85–93.
Snijders, T. a. B., & Bosker, R. J. (1994). Modeled variance in two-level models. Sociological
Methods & Research, 22(3), 342–363. doi:10.1177/0049124194022003004
Spitzer, R. L., Kroenke, K., & Williams, J. B. W. (1999). Validation and utility of a self-report
version of PRIME-MD. JAMA: The Journal of the American Medical Association,
282(18), 1737–1744.
Stanton, A. L., Kirk, S. B., Cameron, C. L., & Danoff-Burg, S. (2000). Coping through
emotional approach: Scale construction and validation. Journal of Personality and
Social Psychology, 78(6), 1150–69.
Stein, M. B., Goldin, P. R., Sareen, J., Zorrilla, L. T. E., & Brown, G. G. (2002). Increased
amygdala activation to angry and contemptuous faces in generalized social phobia.
Archives of General Psychiatry, 59(11), 1027.
Stein, M. B., Walker, J. R., & Forde, D. R. (1996). Public-speaking fears in a community
sample. Prevalence, impact on functioning, and diagnostic classification. Archives of
General Psychiatry, 53(2), 169–174.
Tabibnia, G., Lieberman, M. D., & Craske, M. G. (2008). The lasting effect of words on
feelings: Words may facilitate exposure effects to threatening images. Emotion, 8(3),
307.
Tolin, D. F. (2010). Is cognitive-behavioral therapy more effective than other therapies? A meta-
analytic review. Clinical Psychology Review, 30(6), 710–720.
doi:10.1016/j.cpr.2010.05.003

108
Watson, J. B. (1970). Behaviorism. New York, NY: W.W. Norton.
Wittchen, H. U., Stein, M. B., & Kessler, R. C. (1999). Social fears and social phobia in a
community sample of adolescents and young adults: Prevalence, risk factors and co-
morbidity. Psychological Medicine, 29(2), 309–323.

