


The Research Objective Study of the human genome demonstrates
Study of the human genome demonstrates that nearly all diseases have a genetic/genomic
component (“FAQ About Genetic Disorders,” 2012). Genetics and genomics differ in that
genetics focuses on the structure and function of a single gene, while genomics evaluates all of
the genes and their interactions within an organism (“World Health Organization [WHO]
definitions of genetics and genomics,” n.d.). Clinical applications of genetics and genomics
include pharmacogenomics, screening for genetic variation associated with increased risk of
disease, evaluating if individuals are carriers of genetic variants associated with diseases, and
providing patient counseling and education (“Applying an Implementation Science Approach to
Genomic Medicine,” n.d.). Clinical applications of genetics/genomics include not only
identifying individuals at risk for diseases, but also ameliorating risk through interventions such
as targeted screening and informed therapeutic decision-making.
Because genetics/genomics play a role in disease prevention and health promotion,
screening, diagnosis, treatment selection, and patient-education, all health care providers must
adopt the use of genetics and genomics into clinical practice to provide competent care.
However, despite its importance, evidence indicates genetics and genomics are not being fully
adopted into clinical nursing practice (Calzone, Jenkins, Culp, Bonham, & Badzek, 2013). There
are a number of reasons for this lack of adoption, including lack of knowledge, a lack of
understanding of the relevance, inadequate confidence to use this knowledge to adopt
genetics/genomics into nursing practice, as well as inadequate support from social system(s)
(Calzone, Jenkins, Culp, Caskey, & Badzek, 2014; Camak, 2016).
To increase adoption of genetics/genomics into nursing practice, nursing leaders from
clinical, academic, and research settings worked collaboratively to identify nurses’ roles and
responsibilities in genetics/genomics that are applicable for nurses in all clinical specialties,

roles, and practice settings (Jenkins & Calzone, 2007). This work led to the development of the
Genetics and Genomics Nursing Practice Survey (GGNPS). The GGNPS is an instrument
evaluating nurses’ competency/knowledge, confidence, attitudes/receptivity, and
decision/adoption of genetics genomics into nursing practice; in addition, the GGNPS evaluates
the effect of social systems on each of the previously mentioned variables (Calzone et al., 2012).
The GGNPS can be used both to promote and evaluate the goals of competency initiatives, such
as increasing adoption of genetics/genomics into nursing practice.
The GGNPS was developed from a previously validated instrument assessing the
adoption of genetics/genomics by family physicians (FPs). The GGNPS was revised to reflect
nursing practice and evaluated for test-retest reliability (Calzone et al., 2012, 2016). Although
the FP instrument was evaluated using structural equation modeling and content expert feedback,
the GGNPS has not undergone the same validity evaluation. Thus, it is currently not known if
the GGNPS accurately measures the above domains, in nursing practice. The purpose of this
study was to evaluate the GGNPS for face, content, and construct validity.
The Problem/Research Question
Is the Genetics and Genomics Nursing Practice Survey (GGNPS) a valid instrument to
evaluate registered nurses’ competency/knowledge, confidence, attitudes/receptivity and
decision/adoption of genetics and genomics into nursing practice, and the effect of social
systems?
Definitions
Variables are defined in quotes to provide exact definitions and prevent inadvertent
changes to the definitions of the terms by rephrasing.
Competency/knowledge. Competency was conceptually defined as individuals

providing safe patient care, in accordance with “responsibilities, professional standards,
education, and qualifications” (Axley, 2008, p. 221). Knowledge was conceptually defined as
occurring “when an individual (or other decision-making unit) is exposed to an innovation’s
existence and gains some understanding of how it functions.” Competency/knowledge was
operationally defined as self-reported knowledge of genetics and genomics, genetic risk and
family history assessment. GGNPS: Part 2, Questions 2.1, 2.2, 2.4; Part 4, Questions 1,
2, 3; Part 5, Questions 1, 2; Part 6, Questions 1, 2.
Attitude/receptivity. Attitude is “a relatively enduring organization of an individual’s
beliefs about an object that predisposes his or her actions” (Rogers, 2003, p. 174–175).
Receptivity was conceptually defined as forming a “favorable or unfavorable attitude towards an
innovation” (Rogers, 2003, p. 169). While knowledge is mostly 'knowing' or cognitive,
attitude/receptivity is mostly 'feeling' (Rogers, 2003). Attitude/receptivity was operationally
defined as GGNPS: Part 1, Questions, 1, 2, 3; Part 2, Questions 2, 3.
Decision/adoption. Decision was conceptually defined as activities that lead to a choice
of either adopting or rejecting the innovation; adoption was conceptually defined as use of an
innovation (Rogers, 2003). In the present study, decision/adoption was operationally defined as
self-reported collection and assessment of a family history, as well as self-reported facilitation of
referrals to genetic services. GGNPS: Part 3, Questions 2, 3, 4.
Confidence. “Level of certainty that knowledge about the innovation is accurate”
(Calzone et al., 2012, p. 12). Confidence was operationally defined as responses to confidence-
related questions on the GGNPS: Part 2, Question 1.
Social system. Social system was conceptually defined as the setting or environment
where the innovation was introduced such as the clinical site where nurses are employed

(Calzone et al., 2012). Social system was operationally defined as responses to the social
system-related questions on the GGNPS: Part 7, Questions 1.3, 1.4, 1.5, 1.6, and 1.7.
Delimitations
The present study was a secondary analysis of data collected at 23 Magnet® Recognition
Program hospitals and included a sample of 7,798 registered nurses. These nurses worked in 17
states, from all regions of the United States. Hospitals where the data was collected included a
rural hospital, three children’s hospitals, a Veteran’s Administration, a psychiatric hospital, and
one cancer center (Calzone et al., 2014).
The sample was large and from a variety of clinical sites, but all of the clinical locations
were Magnet® Recognition Program hospitals. A designation based on the American Nurses
Credentialing Center's Magnet Recognition Program, Magnet® hospitals are believed to provide
higher quality of nursing care; a study evaluating nursing care in Magnet® and non-Magnet®
hospitals reported increased patient teaching, more staffing resources, and better communication
in Magnet® hospitals (Kalisch & Xie, 2014). Due to these characteristics, Magnet® Recognition
Program hospitals have an increased capacity to innovate and support pilot programs for new
initiatives (Calzone et al., 2014). As a result, the researchers used purposive sample in selecting
Magnet® Recognition Program hospitals for their sample. The Magnet®
Recognition Program is based on national standards. Therefore, although the sample was only
from Magnet® hospitals, the selected hospitals are more likely to have increased consistency in
infrastructure, educational support, and resources.
Theoretical Rationale
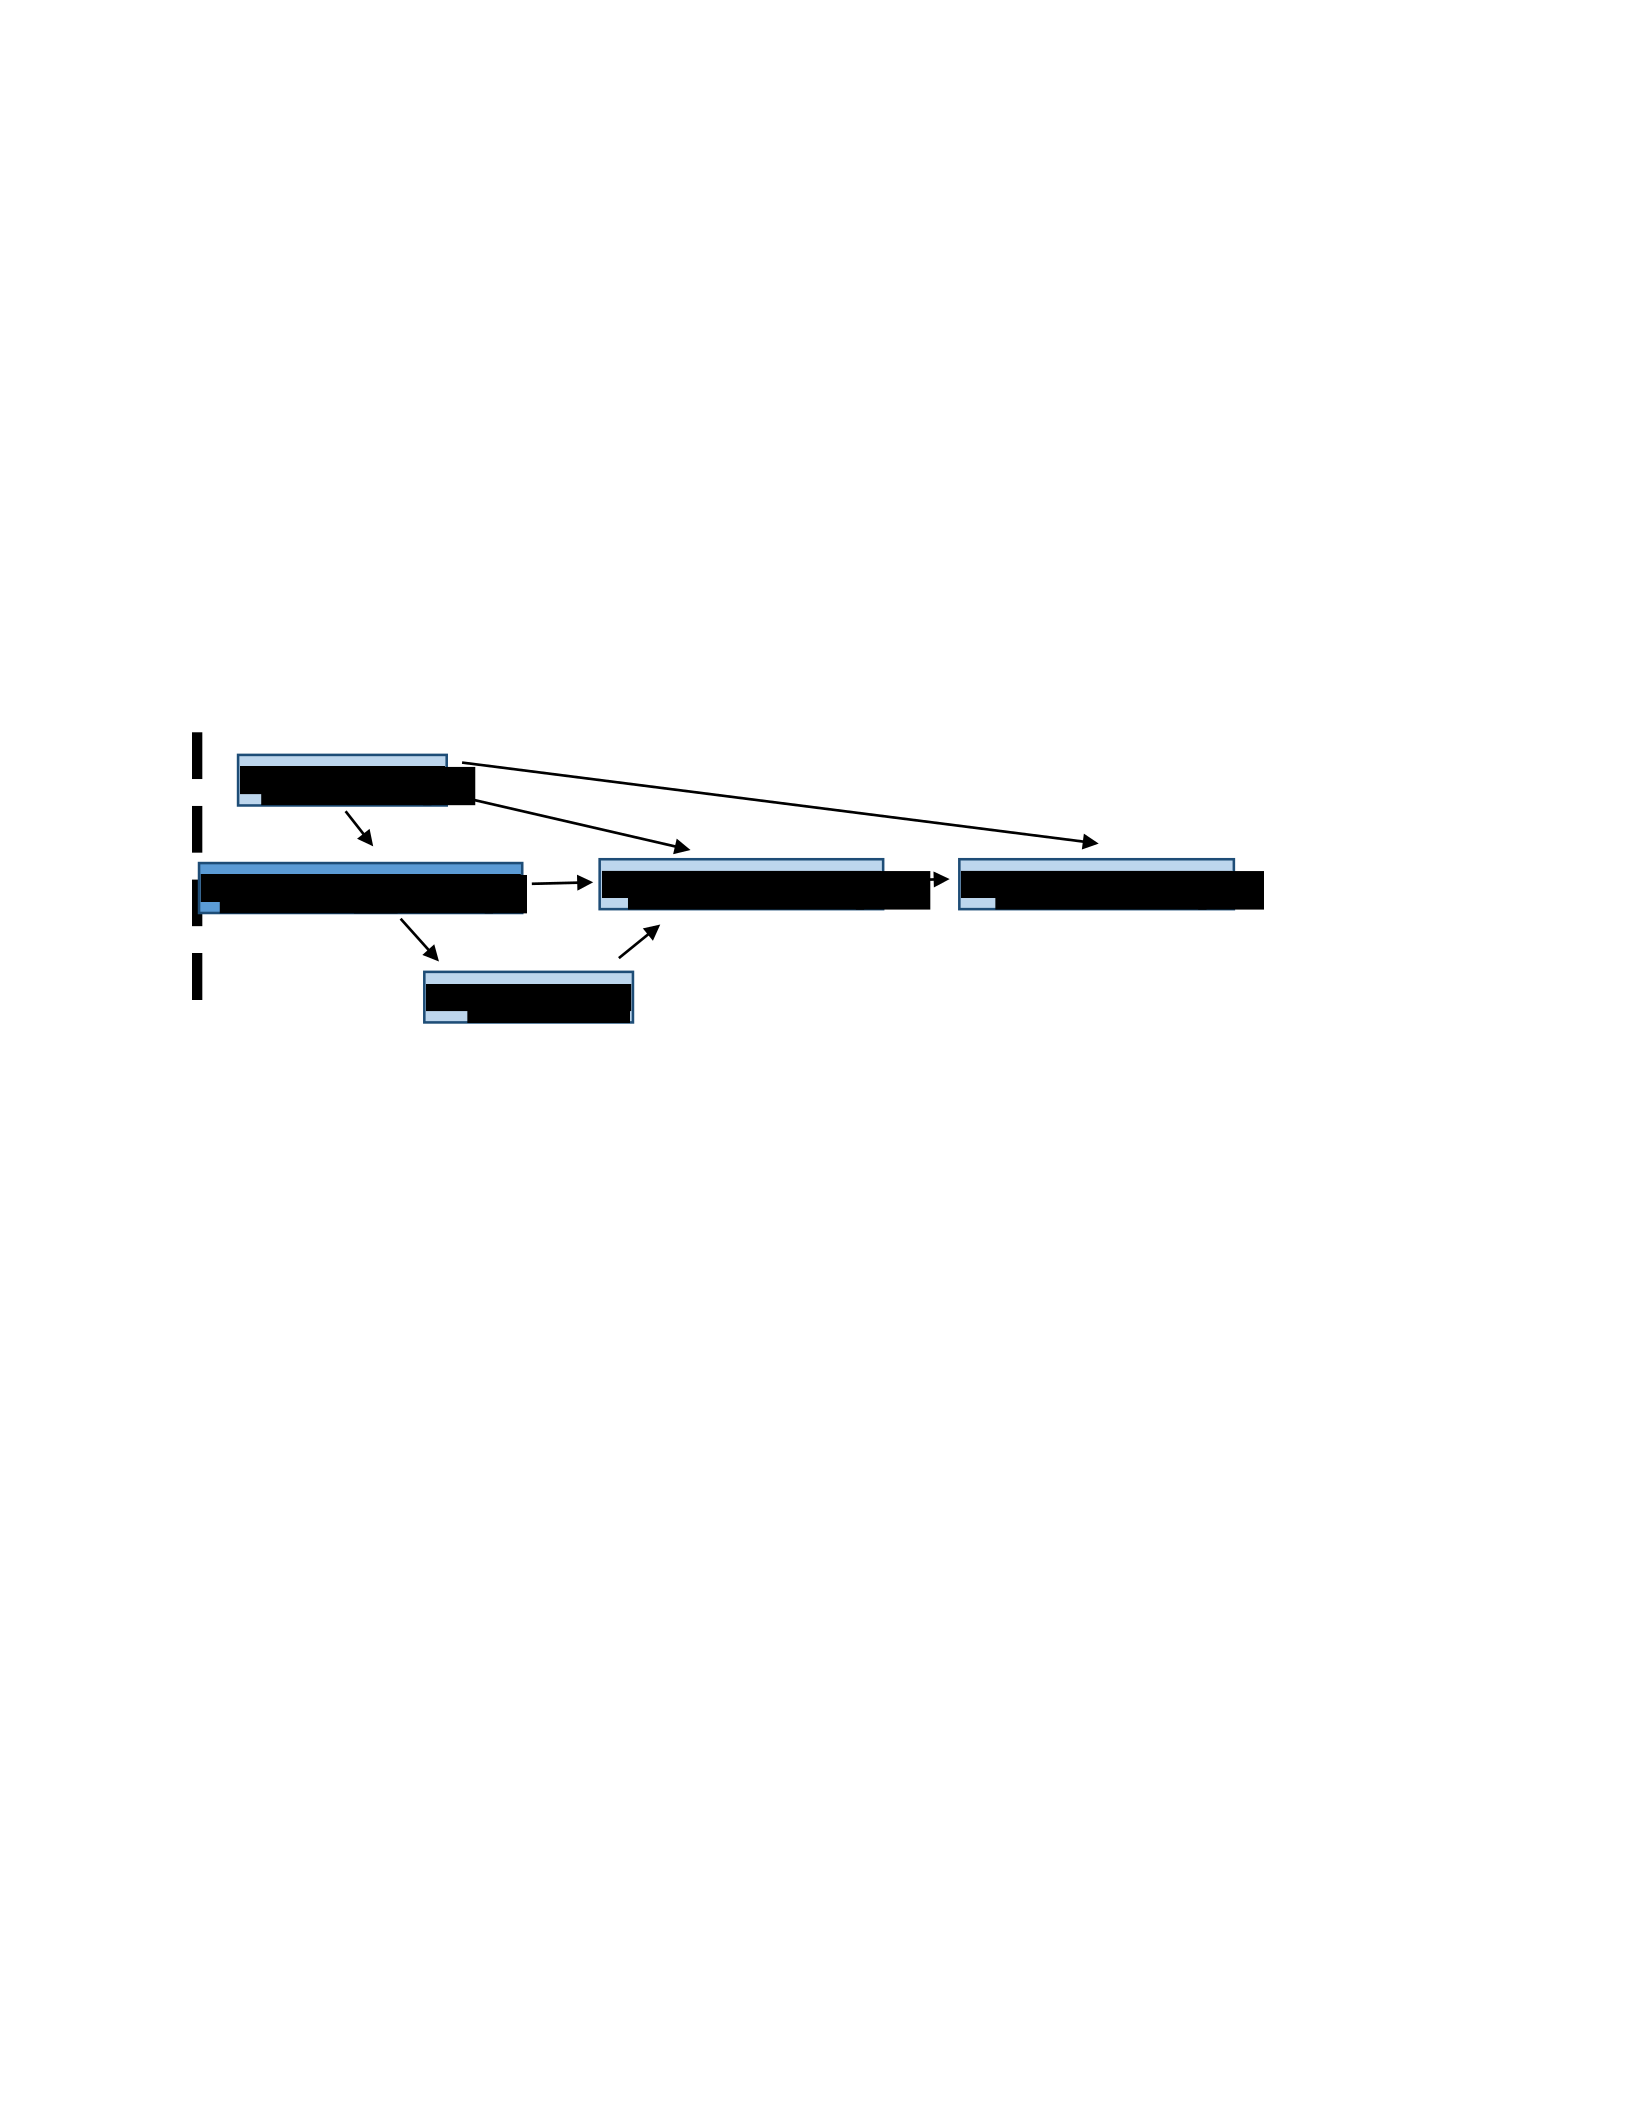
Rogers’ (2003) Diffusion of Innovations (DOI) model provided a conceptual framework
for understanding the adoption of genetics and genomics into clinical nursing practice. Diffusion
of innovations is a process whereby innovations are “communicated through certain channels

over time among members of a social system” (p. 5). According to Rogers, diffusion of
innovation is a process or series of processes whereby an individual (or group) initially acquires
knowledge about an innovation, forms a favorable or unfavorable attitude about the innovation,
and then decides to either adopt or reject it. Rogers also asserted that personality variables affect
adoption; he reported that earlier adopters have a more positive attitude towards change and are
better able to cope with uncertainty and risk. Therefore, this study considered the direct effect of
confidence on attitudes/receptivity. The study also evaluated the indirect effect of confidence on
the outcome variable of adoption of innovations. Likewise, the social system in which the
innovation was introduced was proposed to have both direct and indirect effects. That is, the
social system had a direct influence on all three processes (knowledge, attitude, and adoption),
but also influenced both attitude and adoption indirectly through its direct effect on knowledge
and adoption indirectly through its direct effect on attitude.
Figure 1
Rogers’ DOI model adapted for this study.
Social Systems
Competency
/Knowledge
Attitudes/Receptivity
Decision/Adoption
Confidence

Rogers’ DOI model also includes additional variables such as implementation and
confirmation (see Appendix A); however, this study only evaluated DOI variables measured in
the GGNPS. This did not include the variables implementation and confirmation. Rogers (2003)
defines adoption as full use of an innovation, while implementation is associated with some
uncertainty regarding the innovation and possible reinvention or attempts to modify the
innovation to increase usability. Confirmation is defined as an individual’s personal evaluation
of how they are using the innovation. Further studies evaluating if nurses have continued
uncertainty regarding genetics/genomics or attempt to increase usability by modifying how they
use it in their practice can be used to evaluate implementation and confirmation.
Although molecular scientists and health care researchers have studied genetics and genomics
extensively for a prolonged period of time, they fit the criteria for an innovation in clinical
practice settings because nurses lack knowledge of genetics/genomics and have been slow to
adopt this content into their clinical practice. In addition, the field of genetics and genomics is
continuously expanding with additional molecular discoveries and clinical applications.
Although sequencing of the human genome was completed in 2001, researchers
are still using this information to understand the roles of genes in biological functions, the
interaction between genes and the environment, and how the study of genetic variation can be
applied to health promotion and disease prevention (McAllister et al., 2017). An additional
example is the Precision Medicine Initiative, an effort to pool data from a cohort of one million
people to accelerate clinical research and inform patient care (Collins & Varmus, 2015).
Adoption was the ultimate outcome variable that was evaluated using the GGNPS and is
defined by Rogers (2003) as the full-scale use of an innovation. Rogers’ theory also attempts to
explain how innovations spread among social systems and what factors affect their diffusion.
Rogers stated individuals would adopt an innovation if they believed it has advantages or

usefulness that are not currently available. However, adoption is also affected by a number of
variables, such as the characteristics of the innovation, the adopters, and the system where
adoption is occurring.
GGNPS indicators of adoption of genetics/genomics included collection and evaluation
of a family history, facilitating referrals to specialists when required, and applying knowledge of
clinical genetics and genomics to provide competent and current patient care. These indicators of
adoption were pertinent because they applied to nurses of all levels of academic preparation in a
variety of clinical areas, in different specialties, and with variable access to technology.
Collection and evaluation of a family history, facilitation of referrals, and patient education are
pertinent to nurses caring for clients in in-patient and community settings. As well as nurses
working with patients across the lifespan, using a variety of documentation systems (paper or
electronic), and with varying access to sequencing and genetic technology. Adoption was a key
step because even if an individual has the knowledge to use an innovation, a positive attitude
towards it, and decided to use it -without adoption- the innovation cannot be integrated into
current practice. According to Rogers (2003), the decision to adopt an innovation is the
immediate precursor to adoption of an innovation.
Decision was the portion of the DOI model where individuals engaged in activities that
affected the choice of adopting or rejecting an innovation. However, the decision stage is
difficult to observe and measure because decisions are often internal thoughts (Rogers, 2003).
For this reason, Calzone and colleagues combined decision and adoption into one domain,
facilitating empirical measurement. In this study, decision was considered part of
decision/adoption and is not measured separately.
According to Rogers (2003), decision/adoption is directly affected by one’s
attitudes/receptivity towards the innovation. All innovations engender some degree of

uncertainty for the user, who may be unsure about its utility or may seek reinforcement from
others to form an opinion about an innovation. Positive attitudes/receptivity are critical to
adoption of the innovation because even if an individual had the knowledge or ability to adopt an
innovation, an unfavorable attitude towards may result in rejection. Nurses’ attitudes about
genetics and genomics may affect their adoption of this content into their clinical practice.
GGNPS indicators of attitudes/receptivity included the perceived importance of nurses becoming
more educated about genetics of common diseases and perceived advantages and disadvantages
of incorporating genetics and genomics into nursing practice. These were pertinent indicators of
nurses' attitudes because they evaluated the emphasis and priority nurses allocate to
genetics/genomics. The indicators also evaluated both perceived positive and negative aspects of
adopting genetics/genomics into nursing practice. Rogers (2003) stated that attitude is an
important factor because people will adapt a new innovation if they perceive it to have benefits
over currently existing methods. The GGNPS attempts to evaluate if nurses perceive genetics
and genomics as an important part of their clinical role and as something that facilitates their
nursing practice.
Attitudes/receptivity is directly affected by competency/knowledge.
Competency/knowledge were defined as both awareness of the existence of an innovation and
understanding how it functions (Rogers, 2003). Both components are required for adoption of an
innovation. The knowledge an individual acquires about an innovation not only provides insight
into how the innovation functions, but also affects the attitudes/receptivity the individual may
form about the innovation. An individual may have ample knowledge about an innovation, but if
this competency/knowledge leads to negative attitudes/receptivity regarding the innovation, it
may decrease the likelihood of adoption. Therefore, according to Rogers’ DOI model,
competency/knowledge has a direct effect on attitudes/receptivity and an indirect effect on

decision/adoption. GGNPS indicators of competency/knowledge included questions about
collecting and evaluating a family history, the genetic risks associated with common diseases
(such as cancer, diabetes, and coronary artery disease), genetic make-up (similarities in DNA
sequences), and if diseases are caused by a single gene variant. These were pertinent indicators
of competency/knowledge because they considered gene-environment interaction as well as
interactions between genetic variants. In addition, these indicators included knowledge about the
function of genetic variants and how they affected disease processes.
Although competency/knowledge is the first step of the DOI model,
competency/knowledge is affected by additional factors, such as social systems and confidence.
Social systems were evaluated as an independent variable that may support or hinder adoption of
genetics and genomics into nursing practice. This study evaluated if social systems had a direct
effect on competency/knowledge. It also evaluated if social systems had an indirect effect on
attitudes/receptivity and decision/adoption. Social systems were the environment where an
innovation was introduced, such as a clinical site where nurses were employed (Calzone et al.,
2012). Social systems effect adoption of innovations because they are often the sites where
shared decision making and problem solving occurred (Calzone et al., 2012). Therefore, they
may influence acquisition of knowledge; they may also have an indirect effect on
attitudes/receptivity and decision/adoption. Rogers (2003) reports that the structure of a social
system may be a barrier or facilitator to the spread of innovations. He adds that it may be
difficult to evaluate the role of the social system independently from the characteristics of the
individuals within that system (Rogers, 2003). In the GGNPS, social systems were defined as
supervisory support for nurses using genetic/genomics in their clinical practice, as well as
institutional financial support for continuing education in genetics/genomics. These were
pertinent indicators of social systems because they evaluated both support from

management/administration and financial support for adoption of genetics and genomics into
nursing practice.
In addition, this study evaluated if confidence had a direct effect on attitudes/receptivity.
It also evaluated if confidence had an indirect effect on decision/adoption (through
attitudes/receptivity). Although Rogers does not specifically incorporate confidence into the DOI
model, he does consider how personality variables affect adoption of innovations. The DOI
model indicates a direct effect of personality variables on knowledge, and a corresponding
indirect effect on attitudes/receptivity and decision/adoption. Rogers stated that his analysis of
the effect of personality variables on innovativeness is limited, partly because of the difficulty of
“measuring personality dimensions in diffusion surveys” (Rogers, 2003, p. 289). GGNPS
indicators of confidence were the level of certainty in discussing genetics with patients,
considering which family history information is pertinent in evaluating genetic susceptibility to
disease, obtaining current/reliable information, and facilitating referrals for genetic
testing/counseling. These were pertinent indicators of registered nurses' confidence because they
evaluated confidence in the multi-faceted role of the nurse. Registered nurses’ roles and
professional responsibilities include patient education, collection and interpretation of
information (such as a family history), understanding the benefits/limitations of genetic testing,
facilitating referrals to genetic specialists, and working collaboratively within a professional
team. These roles and responsibilities are within the scope of practice of all nurses, regardless of
academic preparation, specialty, or clinical roles (Jenkins & Calzone, 2007). In summary, the
DOI model conceptualizes how innovations, such as genetics and genomics, pass through social
systems and may or may not be adopted into nursing practice. The DOI model supported the
analysis of how the GGNPS evaluates nurses’ competency/knowledge, attitudes/receptivity, the
effects of confidence and social systems, and use genetics and genomics in clinical practice.

Hypotheses/Research Questions
The hypotheses are derived from the relations between the variables of the proposed
model (see Figure 1).
1. Based on baseline data collected at the initiation of the MINC project, the Confirmatory
Factor Analysis results will show that:
a. GGNPS items Part 2, Questions 2.1, 2.2, 2.4; Part 4, Questions 1, 2, 3; Part 5,
Questions 1, 2; Part 6, Questions 1, 2 comprise the underlying latent variable of
COMPETENCY/KNOWLEDGE.
b. GGNPS items Part 1, Questions, 1, 2, 3; Part 2, Questions 2, 3 comprise the
underlying latent variable of ATTITUDES/RECEPTIVITY.
c. GGNPS items Part 3, Questions 2, 3, 4 comprise the underlying latent variable of
DECISION/ADOPTION.
d. GGNPS item Part 2, Question 1 comprises the underlying latent variable of
CONFIDENCE.
e. GGNPS item Part 7, Questions 1.3, 1.4, 1.5, 1.6, and 1.7 comprise the underlying
latent variable of SOCIAL SYSTEM.
2. Based on baseline data collected at the initiation of the MINC project, the above named
latent variables: COMPETENCY/KNOWLEDGE, ATTITUDES/RECEPTIVITY,
DECISION/ADOPTION, CONFIDENCE, and SOCIAL SYSTEM each statistically
significantly influence integration of genetics and genomics into nursing practice in the
hypothesized model based on Rogers’ DOI:
a. COMPETENCY/KNOWLEDGE of genetics/genomics has a statistically significant
direct effect on one’s ATTITUDES/RECEPTIVITY and CONFIDENCE.
COMPETENCY/KNOWLEDGE has a statistically significant indirect effect on one’s

DECISION/ADOPTION of genetics/genomics.
b. ATTITUDES/RECEPTIVITY has a statistically significant direct effect on one’s
DECISION/ADOPTION of genetics/genomics.
c. SOCIAL SYSTEMS have a statistically significant direct effect on
COMPETENCY/KNOWLEDGE, ATTITUDES/RECEPTIVITY, and
DECISION/ADOPTION and a statistically significantly indirect effect on one’s
ATTITUDES/RECEPTIVITY and DECISION/ADOPTION of genetics/genomics.
d. CONFIDENCE has a statistically significant direct effect on
ATTITUDES/RECEPTIVITY, and a statistically significant indirect effect on
DECISION/ADOPTION of genetics/genomics.
3.Does the GGNPS meet the threshold for face validity (as defined by ease of understanding
and ability to apply the instrument to nursing practice by RNs)?
4.Does the GGNPS meet the threshold for content validity based on evaluation by content
experts and analysis of a content validity index (CVI)?
Need for the Study
Genetics and genomics have the potential to change how health care providers screen for,
diagnose, and treat diseases; as well as how we intervene to reduce disease risk. Identification of
genetic variants can be used to determine genetic risk factors and conduct targeted screening; it
can also be used to identify effective pharmacological agents and therapeutic doses.
Understanding and integrating genetics/genomics into clinical practice will allow nurses to
provide evidence-based care to improve patient outcomes; it will also promote evidence-based
use of genetic/genomic information and technology. The GGNPS can be used in educational and
clinical settings to evaluate nurses' use of competencies in genetics and genomics. It is also used
to evaluate registered nurses’ attitudes, receptivity, knowledge, and confidence in genetics and

genomics. Information gathered from the GGNPS can be used to identify knowledge gaps,
create targeted educational initiatives, and/or identify barriers to incorporating genetics and
genomics into clinical practice. In addition, evaluation of nurses’ adoption of genetics and
genomics creates accountability for this content in nursing practice. Genetics and genomics play
an important role in the leading causes of mortality and morbidity and must be a part of
competent, evidence-based nursing practice aiming to improve patient outcomes. The GGNPS
has been evaluated for test/retest reliability; however, validity has yet to be established. As
clinical knowledge advances, new competencies must be added to nursing practice to promote
safe and accountable patient care (Calzone et al., 2014). Validity testing of the GGNPS can
increase its utility as part of a strategic pathway to achieve genetic/genomic competency among
RNs.

Chapter II
Review of the Literature
This chapter discusses how the variables competency/knowledge, confidence,
attitudes/receptivity, and the social system affect decision/adoption of genetics and genomics into
nursing practice. The chapter also explores relations among the variables in the proposed path
model. Specifically, it has been proposed that the adoption of genetics and genomics into one’s
practice is directly dependent upon one’s attitude towards this innovation and the social system’s
support for one’s decision. In turn, one’s attitude is directly influenced by one’s
competency/knowledge, confidence and the social system's support. Finally, one’s confidence is
directly influenced by one’s knowledge and knowledge is directly influenced by the social
system. Due to the pervasive nature of social systems (see model below) its effects are discussed
following each relevant variable.
Decision/Adoption
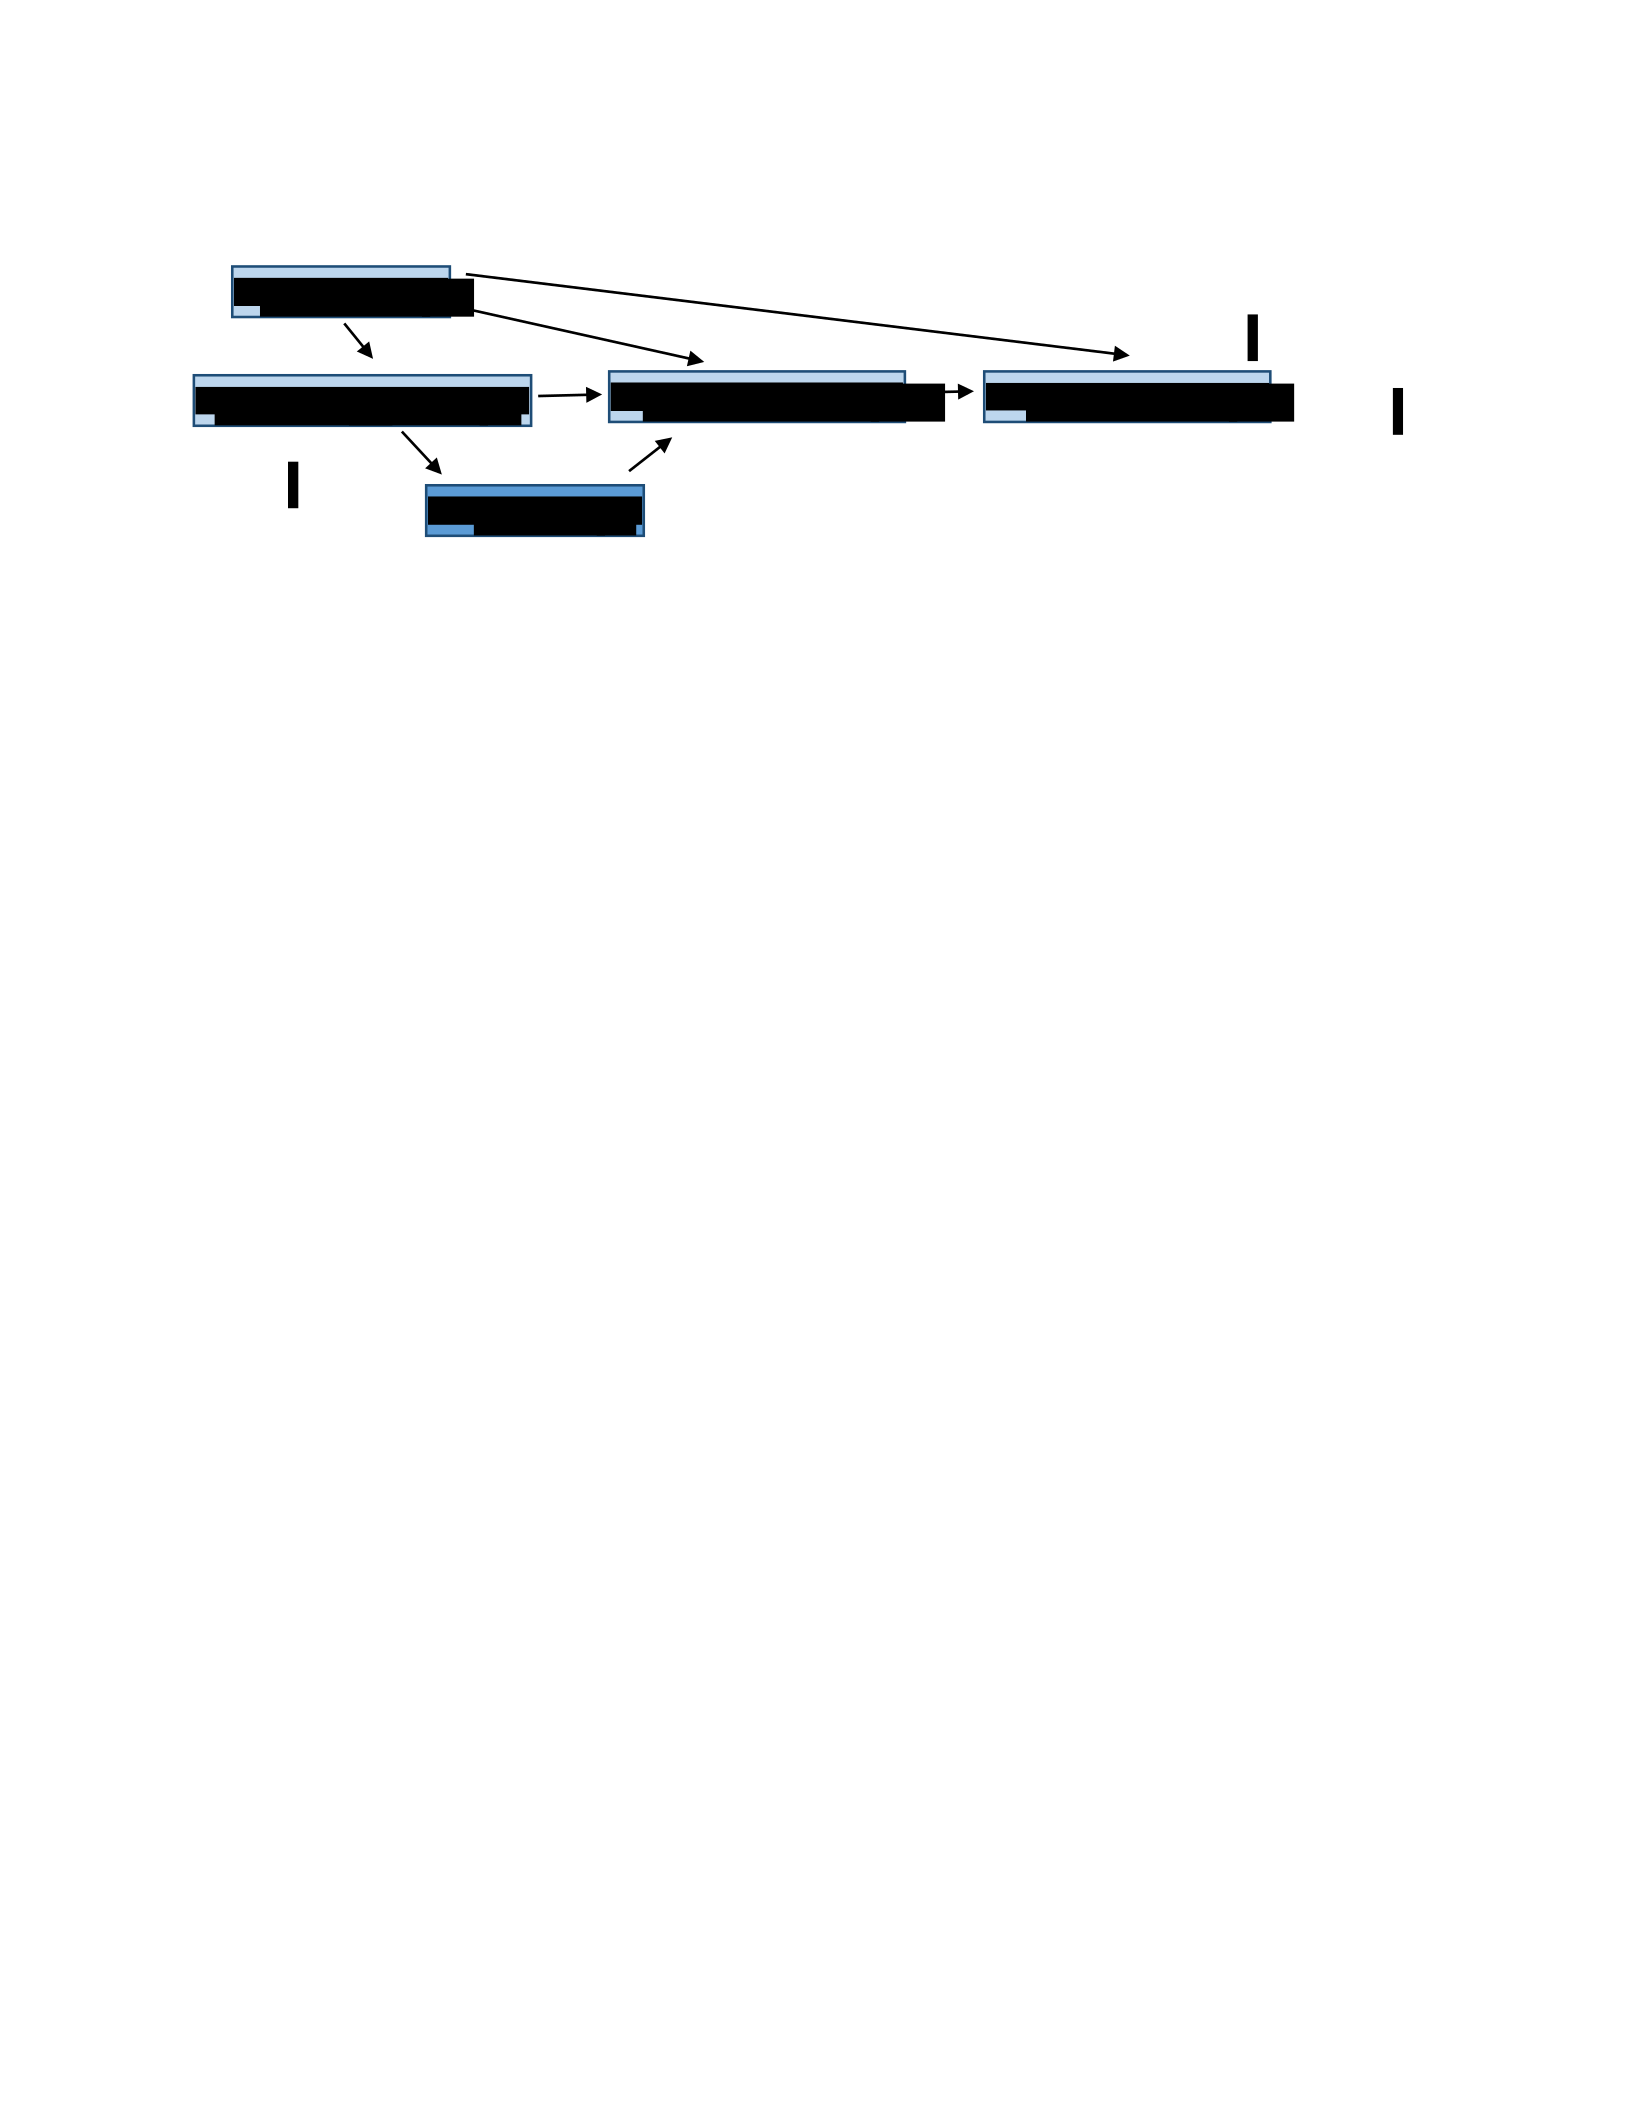
Figure 2
Variables affecting Decision/Adoption in the adapted model.
Adoption was defined as use of the innovation (Rogers, 2003). For the purpose of this
study adoption was defined as considering and making referrals to genetics specialists, collecting
a personal/family history, and obtaining physical assessment data (Jenkins & Calzone, 2007;
Jenkins, Woolford, Stevens, Kahn, & McBride, 2010). Thus, the GGNPS measured adoption of
Social Systems
Competency
/Knowledge
Attitudes/Receptivity
Decision/Adoption
Confidence

genetics/genomics into one’s nursing practice, among nurses who actively see patients. Adoption
was measured by self-report of collection and use of family history information within the past
three months. The three-month time frame demonstrates current and consistent use. Information
from the family history was used to provide recommendations to patients and/or to facilitate
clinical decisions, as well as providing the basis for referrals to genetic specialists (Calzone et al.,
2012).
Family history evaluation is a powerful predictor of an individual’s risk of disease
because relatives share genetic makeup and environmental interactions (David et al., 2015). In
fact, in oncology, aside from an early onset of cancer, family history is the most important
indicator of hereditary cancer risk (Weitzel, Blazer, MacDonald, Culver, & Offit, 2011). For
example, a meta-analysis reported that even one family member with pancreatic ductal
adenocarcinoma may increase the patient's risk by 80% (RR = 1.80; 95% CI: 1.48-2.12; n =
6,568) (Permuth-Wey & Egan, 2009).
Similarly, Do and colleagues (2012) used quantitative modeling to show that family
history evaluation is particularly effective for highly prevalent, heritable conditions such as atrial
fibrillation and coronary artery disease. Quantitative modeling included standard liability
threshold models and models of variance in heritability explained by family history and single
nucleotide polymorphism (SNPs). SNPs are differences in DNA sequences based on one
nucleotide (A, T, C, or G); substantial changes in clinical outcomes can result from variation in
such small segments of DNA. The models illustrated that, in common heritable conditions,
family history evaluation may explain approximately 20-30% of disease heritability. This is as
effective as currently available molecular SNP models. For example, coronary artery disease has
more heritability explained by a complete family history (f = 26.3%) than by SNPs (f = 6.9%)
with f as the proportion of heritability explained by family history. In addition, lifetime

morbidity risk is K = 0.402, and heritability of liability is h²L = 0.49 (where h²L indicates the
proportion of variance explained by the substitution of one allele for another allele of the same
trait) (Do et al., 2012). Family history assessment is, therefore, an important tool in clinical
nursing practice to identify increased genetic/genomic risk for a number of diseases.
Furthermore, family history collection is not dependent on availability of technology or
insurance status, and it is possible to obtain in most clinical settings.
All nurses should know when and how to refer clients to a genetic specialist. Referrals
may be considered based on family history results, to provide additional genetic/genomic
information, genetic testing, interpretation of test results, and/or to discuss available services
(American Association of Colleges of Nursing [AACN], 2008). A referral may also be
considered if one or more family members are diagnosed with a condition that may have a
genetic component or for reproductive genetic testing, especially for individuals in certain ethnic
groups (Hampel, Bennett, Buchanan, Pearlman, & Wiesner, 2015). Genetic specialists can also
discuss the benefits or limitations of genetic testing, the results of genetic testing, and possible
genetic causes of diseases.
Shields and colleagues (2010) illustrated the importance of genetic referrals. They found
that maturity-onset diabetes of the young (MODY) is often misdiagnosed as diabetes mellitus
type 1 or 2 because MODY diagnosis can only be confirmed via molecular genetic testing. As a
result, referrals to genetics specialists are vital for correct diagnosis. They reported substantial
positive correlation between prevalence of MODY and rates of referrals for genetic testing.
Clinicians from England referred 1,712 patients for genetic testing and the mutation detection
rate was 27.4% in this group. In contrast, clinicians from Northern Ireland referred only 30
patients and the mutation detection rate was 23.3% in this group (Shields et al., 2010).

Therefore, the rate of detecting mutations was similar in both countries, but increased referrals
for testing increased the number of people who were correctly diagnosed with MODY.
Open, patient-centered communication is another key component of providing quality
nursing care (Lamiani & Furey, 2009). Adoption of genetics and genomics into nursing practice
includes discussing information with patients/families and providing patient education (Calzone
et al., 2012). Registered nurses assess patients’ understanding, perceptions, and beliefs regarding
genetic and genomic information. Nurses can also identify patients who will benefit from
additional information, provide patients with credible, current, and accurate sources of
information, and educate patients about interpretation and use of this information (Jenkins &
Calzone, 2007). Patient education and counseling are vital components of genetic testing
because they are means to inform patients of how a test is conducted, its risks and benefits,
sensitivity/specificity, how results are interpreted and their clinical significance, and whether
follow-up is required.
However, despite the benefits of patient counseling and education, they are performed at
varying frequencies. For example, a study of 39 clinics providing assistive reproductive
technology revealed significant variation of genetic counseling and education practices for
preimplantation genetic diagnosis (PGD) (Girardet et al., 2016; McGowan, Burant, Moran, &
Farrell, 2009). This testing can identify conditions such as Down Syndrome, Huntington’s
Disease, Sickle Cell Disease, and many others. In instances where testing was recommended,
patient counseling was not done consistently. Genetic counseling was required for all such
patients at 56% (n = 22/39) of the clinics, 15% (n = 6/39) of clinics required counseling most of
the time, and 26% (n = 10/39) some of the time (McGowan et al., 2009). Counseling was
provided by certified genetic counselors, physicians, and nurses. The study stressed the
importance of pretest counseling because identification of genetic variants associated with

diseases may lead to significant anxiety among patients. This study also highlights the important
role of nurses in providing genetic counseling because nurses were the most likely to obtain
consent at 17% (n = 6/39) of the clinics for in vitro fertilization procedures, followed by the
patient’s physician at 14% (n = 5/39), or the IVF-specific educator at one (n = 1/39) clinic
(McGowan et al., 2009). Nurses provided genetic counseling and procedure consent for many
patients, supporting patient education, and discussion of genetic/genomic interventions as part of
adoption of genetics/genomics into nursing practice.
Health care providers also play an important role in patient and family education. In
newborn screening for cystic fibrosis and sickle cell disease, nurses and physicians educate
parents about the implications of having a child affected with a condition as well as being a
carrier. Furthermore, health care providers are also a source of education and support when
parents eventually decide to inform their children of their carrier status. A national,
crosssectional, qualitative study in England used semi-structured interviews (n = 67) to explore
experiences of parents receiving positive carrier results for their children following newborn
screening (Ulph, Cullinan, Qureshi, & Kai, 2014). The study also provided insight into parent’s
views of how to inform their children of carrier status. Results indicated that parents wanted to
inform their children to empower them. Many parents focused on reproductive implications and
considered informing their children based on life events such as becoming sexually active.
However, it was difficult for parents to identify a specific age to inform their children. Parents
who were unsure about how to inform their children thought health care professionals would
provide the information. Parents who wanted to inform their children themselves emphasized the
complexity of issues and hoped health care professionals would provide additional education and
support. The study highlighted the important role that healthcare providers, including nurses,
play in ongoing patient and family education regarding the implications of genetic testing.

However, despite the known importance of consistent use of genetics/genomics in nursing
practice, rates of adoption are consistently low. A study using the GGNPS included a
convenience sample of 619 registered nurses, 359 of whom reported actively seeing patients,
self-selected to participate via recruitment on the American Nurses Association (ANA) website;
only 6% (n = 22/359) of participants reported always, and 12% (n = 45/359) often, taking a
family history (Calzone et al., 2013). A follow-up study including 7,798 registered nurses from
17 states and all regions of the U.S. reported similar results. Only 4.1% (n = 204/4,979) of
participants reported collecting a complete family history in the past 3 months; meanwhile,
92.8% (4,563/4,913) reported they rarely or never facilitated referrals to genetics services.
Reported response rates (4,979 and 4,913 respectively) varied due to the number of participants
answering each question (Calzone et al., 2014). Although both of those studies use the GGNPS,
which has not yet been tested for validity, the findings consistently demonstrate low adoption of
genetics/genomics among nurses.
Social systems and decision/adoption. Social systems are proposed to directly affect the
adoption of genetics/genomics into nursing practice (Calzone et al., 2012). Norms of the social
system establish patterns of behavior among its members (Rogers, 2003). According to Rogers
(2003), social systems are interrelated units collaborating in a joint-problem solving effort to
accomplish a common goal. Unit members may be individuals, groups or organizations.
Moreover, social systems serve as a guide or standard for expected behaviors.
Do and colleagues (2012) study concerning the importance of family history taking
highlighted the usefulness of the online, interactive family assessment tools, such as “My Family
Health Portrait,” developed by the Surgeon General and National Human Genome Research
Institute (NHGRI). It is notable that government initiatives often create incentives for health
care institutions to focus on specific topics in clinical care. Do and colleagues point out that this

online tool may guide health care institutions to create a social climate promoting collection of
family history and the interactive format promotes ease of use. The authors also discuss that
even small improvements diagnosing conditions with the use of family history may have
farreaching benefits when applied to a large population. They urged public health initiatives that
allocate resources for using family history disease prevention and screening. Highlighting the
importance of family history evaluation is key to create social system support among health care
organizations.
However, a further challenge for the collection and use of family history information is
electronic documentation; EHRs often do not have a designated location to document and refer
back to family history information (Kho et al., 2011). As a result, nurses are unsure of where to
initially document the information or how to find family history information that is located in an
electronic health record.
Girardet and colleagues (2016) noted that no standardized protocols were available
regarding the use of PGD in reproductive medicine. They suggest that this may be a social factor
adversely affecting standardization of informed consent procedures among clinics because
centers are developing their own clinical procedures. As use of PGD grows, health care
providers are more in need of guidelines from professional organizations. Guidelines could help
create a standard system providing informed consent for patients.
Finally, Shields and colleagues (2010) discussed a number of social system factors that
may prevent correct diagnosis of MODY including the cost of genetic testing. Some health care
institutions may consider genetic testing cost-prohibitive; this may also vary with how
institutions are reimbursed. Additional social system factors include research foci. Areas with a
stronger research interest in MODY have higher rates of diagnosis and referral. Social systems
in those health care organizations may provide additional support because research interests align
with clinical practice. In summary, social systems can directly affect nurses’ adoption of
genetics/genomics through encouraging referrals, family history taking and counseling.
Competency/knowledge is the next variable presented because knowledge about an innovation is
closely tied to its adoption.
Competency/Knowledge
Figure 3
Variables affecting Competency/Knowledge in the adapted model.
Rogers (2003) defined knowledge as occurring “when an individual (or other
decisionmaking unit) is exposed to an innovation’s existence and gains some understanding of
how it functions” (p. 169). Knowledge may be passive or active; individuals may incidentally
discover some information about an innovation and then actively seek information. In the DOI
model shown above, knowledge directly affects attitudes/receptivity; gaining knowledge about
an innovation affects the formation of a favorable or unfavorable attitude towards it. This occurs
because knowledge about an innovation includes information about its existence and information
about how it would be used in an individual’s social system. Deciding to adopt or reject an
innovation is both an information seeking and information processing activity. Thus establishing
the indirect relation between knowledge and decision/adoption, through attitudes/receptivity.
Social Systems
Competency
/Knowledge
Attitudes/Receptivity
Decision/Adoption
Confidence

Individuals gain knowledge about an innovation, formulate an attitude, and decide to adopt or
reject it. Genetic/Genomic knowledge acquisition ideally begins during basic nursing education.
However, nursing schools have been slow to integrate genetics/genomics into their curricula
(Jenkins & Calzone, 2014; Read & Ward, 2016).
The Health Resources and Services Administration (HRSA) (2000) stressed the
importance of integrating genetics content into nursing curricula to prepare nurses to apply this
knowledge to clinical practice. Despite this, in the five years that followed, only 30% of nursing
schools included such content (Edwards, Quannetta, Maradiegue, Macri, & Sitzer, 2006; Prows,
Calzone, & Jenkins, 2006). A number of factors contributed to this slow adoption into nursing
curricula and corresponding slow adoption into nursing practice: many nurses considered
genetics/genomics a subspecialty and not needed for routine practice; the long list of
competencies at the time was daunting, making it unclear what nurses needed to know;
insufficient numbers of faculty were prepared to teach the content; and state boards did not
consider this knowledge a requirement for licensure or relicensure, therefore there was little
impetus to change curricula (Jenkins & Calzone, 2007, 2014; Read & Ward, 2016).
Currently, the “Essentials of Genetic and Genomic Nursing: Competencies, Curricula
Guidelines, and Outcome Indicators” (2009) are a clear and concise source of competencies
applicable to nursing practice, education, and research. They were used by the American
Association of Colleges of Nursing (AACN) as the foundation for integrating genetics/genomics
into the revised Essentials of Baccalaureate Education for Professional Nursing Practice (2008)
and The Essentials of Master’s Education in Nursing (2011). The AACN Essentials provide the
basis for the Commission on Collegiate Nursing Education (CCNE) accreditation standards for
baccalaureate and masters programs (Jenkins & Calzone, 2014). Despite these developments,
nursing faculty are still struggling to integrate genetics/genomics into nursing curricula.

This is evidenced by a small study (Jenkins & Calzone, 2014), evaluating preparation of
nursing faculty to champion integration of genetic/genomics into their curricula. The study
included a yearlong educational initiative and formation of support networks for nursing faculty
champions to act as change agents at their schools. Prior to beginning the educational initiative,
91% (n =18/20) of the faculty, from all regions of the US except the Northwest, reported a lack
of genetics/genomics knowledge. This is despite the mean of 13.8 years faculty experience
(range of 2-38 years), and the fact that 65% (n = 13/20) of participants had doctoral degrees
(Jenkins & Calzone, 2014).
A larger study, conducted by Read and Ward (2016) included 495 nursing faculty
members from across the U.S also reported a lack genetics/genomics knowledge among nursing
faculty. The faculty completed the Genomic Nursing Concept Inventory (GNCI), a tool
evaluated for reliability and content validity. The GNCI evaluates knowledge related to genome
basics, mutations, inheritance, and genomic health. The mean score was 14.93 (SD = 5.31) or
48% correct. The authors reported that the results were similar to those of nursing students,
mean score of 47% correct. Factors related to a higher score among faculty included doctoral
level education, completion of a genetics course, previously teaching a genetics course, or
teaching genetics content in a related course.
Furthermore, Jenkins and Calzone (2012) reported that, despite agreeing with the
importance of incorporating genetics and genomics into the nursing curriculum, a sample of 167
nurses at AACN and Sigma Theta Tau International meetings reported a limited capacity to
incorporate genetics and genomics into their own curricula. Of the participants, 82% had a
masters or doctoral degree, and 81% were aware that the AACN incorporated genetics/genomics
into the Baccalaureate Essentials. However, 46% rated their genetic/genomic knowledge as
‘low’ and 25% as ‘very low’ (Jenkins & Calzone, 2012). The limited preparedness of faculty

contributes to decreased opportunities for nursing students to gain knowledge about the topic.
Moreover, nursing education does not stop at graduation. Genetics/genomics is a complex and
rapidly evolving science. Nurses need continuing education to maintain current clinical practice
and continuing education is even more important for nurses who have not yet been introduced to
genetics/genomics content. Up to date educational materials are available through the
International Society of Nurses in Genetics (ISONG), the National Human Genome Research
Institute (NHGRI), and the Genetics/Genomics Competency Center (G2C2) (a peerreviewed
resource repository for health care professionals), among others. Peer reviewed publications and
continuing education credits are additional sources of such information.
Despite this, a systematic review by Skirton and colleagues (2012) reported a lack of
genetics/genomics knowledge among practicing nurses. Authors reviewed 269 articles and
included 13, to evaluate nurses’ knowledge, experience, perceived relevance, and confidence
using genetics/genomics in their nursing practice. In none of the 13 reviewed studies did nurses
demonstrate adequate levels of knowledge, as defined by knowledge required to fulfill core
nursing competencies in genetics/genomics. However, one limitation of this review is that
studies varied in how they evaluated nursing knowledge. Thus, though there is a seeming lack of
genetics/genomics knowledge among nurses, it is possible that this may in part be due to the lack
of a valid and reliable instrument to accurately or consistently assess nurses’ knowledge. The
GGNPS can be used to address this research gap by evaluating nurses’ knowledge of
genetics/genomics and promoting knowledge acquisition by identifying areas of knowledge
deficit that can be used to guide educational initiatives.
The GGNPS includes items assessing participants’ knowledge about how to collect a
family history and the role of the nurse in counseling patients about genetic risks. Knowledge
items also assess participants’ perceptions of the relevancy of genetic risk to common diseases

such as breast cancer, coronary heart disease, diabetes, colon cancer, and ovarian cancer. Items
also assess use of family history information and genetic testing to support clinical
decisionmaking. Additional items evaluate nurses’ knowledge of DNA structure, the role of
single gene variants in causing common diseases, and awareness of Essential Nursing
Competencies and Curricula Guidelines for Genetics and Genomics (Calzone & Jenkins, 2011).
It is imperative that there is an awareness of these competencies because they define what all
registered nurses need to know about genetics/genomics, regardless of academic background,
practice setting, role, or specialty (Consensus Panel on Genetic/Genomic Nursing Competencies,
2009).
An additional component of the GGNPS is evaluation of both self-reported and objective
knowledge. Self-reported knowledge is what nurses say they know about the topic. Objective
knowledge is measured by assessing actual knowledge about family history collection and
knowledge of genetic risk associated with common diseases. A deficit of objective measures of
knowledge of genetics/genomics is an important limitation in available research regarding
nurses’ knowledge of this content because self-reported knowledge may differ from objective
measures of knowledge.
For example, Skirton and colleagues (2012) reported that 10 out of 13 reviewed studies
evaluated only self-reported knowledge of genetics/genomics and overall nursing knowledge was
poor. Upon close inspection of the individual studies it was found that, Spruill and colleagues
(2009) reported that 56% (n = 43/77) of nurses rated their genetics knowledge as fair or poor;
while 43% (n = 33/77) reported their knowledge as good. In the study conducted by Tomatir and
colleagues (2006), only 4.2% (n = 2/47) of nurses self-reported that they were knowledgeable
about topics such as autosomal recessive disorders and human genetic diseases, and had
insufficient knowledge about ethical issues in genetics or genetic counseling.

Interestingly, although a very limited number of studies tested nurses’ objective
knowledge of genetics/genomics (as opposed to self-reported knowledge), objective measures of
knowledge often yielded higher scores than self-reported knowledge. In one study, 81.4% (n =
777/955) of nurses chose the correct definition of a mutation and 81.5% (n = 782/960) correctly
answered that men can inherit genetic mutations related to breast cancer (Bottorff et al., 2005).
These authors concluded that self-reported knowledge of genetics/genomics significantly differed
from objective knowledge about the topic. In addition, there were few studies evaluating both
self-reported and objective measures of nurses’ knowledge of genetics/genomics. Thus, the
GGNPS has the capacity to contribute much needed data regarding both self-reported and
objective measures of knowledge of genetics/genomics among nurses.
Social systems and competency/knowledge. Social systems may affect knowledge
acquisition of genetics/genomics among nurses via the emphasis nursing curricula and health
care organizations place on such knowledge. Beginning in 2010, the CCNE accreditation
standards for baccalaureate nursing schools mandated genetics/genomics content based on the
AACN revision of the revised Essentials of Baccalaureate Education for Professional Nursing
Practice (2008). In 2011, the ACCN published the revised Essentials of Mater’s Education in
Nursing, which also included genetics/genomics content. In addition, the AACN noted that
genomics is one of the sciences creating a foundation for nursing practice in the Essentials of
Doctoral Education for Advanced Nursing Practice (2006). As the organizations that set the
standards for nursing education and accrediting bodies continue to highlight the role of
genetics/genomics, this will create greater impetus for curricular change among all levels of
nursing education (Jenkins & Calzone, 2014). However, it is notable that associate degree and
practical/vocational nursing programs are not mandated to include genetics/genomics content,
based on accreditation standards from the NLN-CNEA and NCSBN (“Commission for nursing

education accreditation: Accreditation standards for nursing education programs,” 2016).
Furthermore, NCSBN (2012) is considering a new model of national accreditation for nursing
programs beginning in 2020, therefore additional follow up is required to evaluate if
genetics/genomics content will be included in national accreditation standards.
Jenkins and Calzone (2014) highlighted the role of social systems on knowledge in the
aforementioned nursing faculty champion initiative study. Adoption of the content required, not
only faculty expertise but, support from university administrators and peer networks. For
example, university deans and program directors championed faculty applicants by writing letters
of support and a peer support network was an additional source of social system support.
Faculty champions could discuss questions with nurses who were experts in genetics/genomics.
Support and education from initiatives such as the faculty champion program can help faculty
reach the above-mentioned educational goals outlined by the ACCN and CCNE.
In relation to nursing practice, Kirk and colleagues (2008) identified social systems as a
potential facilitator or barrier to gaining knowledge about genetics/genomics. An example of
social systems facilitating knowledge acquisition is institutions that support continuing education
for nurses. However, in a previously mentioned study Calzone and colleagues (2014) note that,
following licensure, 86.8% (n = 4,594/5,294) of participants reported they had not completed any
courses focusing on genetics/genomics. Allowing time during work hours to complete
genetics/genomics-based courses or educating staff about available courses are potential
facilitators or barriers to knowledge acquisition of this content among nurses.
Competency/knowledge and attitudes/receptivity. Competency/knowledge is
hypothesized to directly affect attitudes/receptivity because knowledge about an innovation
affects the formation of favorable or unfavorable attitudes towards it (Rogers, 2003). Carroll and
colleagues (2009) reported that, an educational intervention positively affected the attitudes of
participants in a small multidisciplinary workshop that included nurses, nurse practitioners,

physicians, and other health care providers. Following the interactive workshop and educational
modules, there was a statistically significant increase in the number of participants agreeing that
genetic testing was beneficial in the management of adult-onset diseases (p= .031), using the
McNemar test for matched categorical variables (Carroll et al., 2009). While the sample size was
small, managers and administrators among those organizations cited the participants as leaders in
their departments. Thus, it is likely that the impact on these leaders’ attitudes towards
genetics/genomics’ usefulness will carry over to their institutions and subordinates.
Similarly, in a previously mentioned study, Calzone and colleagues (2014) empirically
demonstrated the relation between Competency/knowledge and attitudes/receptivity. Nurses (n =
7,798) who attended a genetics course following licensure were more likely to report that
education about genetics/genomics was very important (p <.001, n = 7,798) and strongly agreed
that nurses have a key role in patient counseling regarding genetic risks (Calzone et al., 2014).
Competency/knowledge and decision/adoption. The Calzone and colleagues (2014)
study also reported that educational level (associate to doctorate) affected nurses’ collection of
family history information, demonstrating the relation between competency/knowledge and
decision/adoption, through attitudes/receptivity. Furthermore, nurses who attended a genetics
course following licensure were more likely to ‘always’ or ‘often’ collect family history
information (p <.001, n = 7,798) (Calzone et al., 2014). This may be because the increased
knowledge resulted in favorable attitude towards genetics/genomics and thus increased the
likelihood of their adopting this content into their clinical practice.
In a similar vein but in a non-genetics/genomics context, Cook and colleagues (2013)
studied the effect of an educational intervention on the knowledge, confidence, attitudes, and
clinical practice of nurses caring for patients with mild traumatic brain injury (mTBI). New
clinical recommendations promote ‘brain rest’ and vigilant symptom assessment to promote

recovery. ‘Brain rest’ includes avoiding physical exertion, television, and some electronic
devices. Twenty-eight nurses participated in a quasi-experimental one group pre-test, post-test
study. Knowledge of post-concussion symptoms, symptom assessment, and ‘brain rest’
guidelines were evaluated with an instrument deemed to have content and face validity. An
educational intervention was developed based on the CDC guidelines for head injury.
Following the educational intervention, trauma nurses reported being better able to
identify interventions required to decrease symptoms following an mTBI (χ² = 6.125, p = .001)
(knowledge)(Cook et al., 2013). In assessing nurses’ attitudes, 96% (n = 24/25) of the
participants reported the educational intervention increased their understanding of the importance
of symptom assessment and brain rest guidelines (attitudes). However, while between-group
analysis showed that specialty resource unit nurses (who float between the emergency
department and acute in-patient units) increased their use of mTBI symptom assessment
(5086%), only 52% of the participants reported using mTBI symptom assessment in their clinical
practice (adoption) (Cook et al., 2013). While the study reported a mixed effect of
competency/knowledge on decision/adoption, through attitudes/receptivity, a number of variables
were self-reported and not verified in medical records. Competency/knowledge may also affect
confidence because acquisition of information and ability to apply it may increase confidence.
The following section will explore the variable of confidence and the relation between
competency/knowledge and confidence, as well as confidence and attitudes/receptivity.
Confidence
Figure 4
Variables affecting Confidence in the adapted model.
Calzone and colleagues (2012) defined confidence as the “level of certainty that
knowledge about the innovation is accurate” (p. 12). While Rogers (2003) did not directly
address confidence as a variable that affects adoption of innovations, he did discuss the effect of
personality variables. Rogers stated that earlier adopters are better able to cope with uncertainty
and risk. Benner’s (1984) research about confidence in nursing paralleled many characteristics
described by Rogers. Benner (1984) noted that experienced nurses have more confidence in their
abilities and are more capable of managing difficulties/challenges. As nurses come closer to
becoming experts, they increase their critical thinking ability; critical thinkers exhibit a number
of characteristics including confidence, flexibility, and open-mindedness (Benner, Hughes, &
Sutphen, 2008). This parallels Rogers’s (2003) theory that individuals who can cope with
uncertainty and risk are more likely to adopt innovations. Therefore, this study evaluated the
direct effect of competency/knowledge on confidence as well as the direct effect of confidence
on attitudes/receptivity and the indirect effect of confidence on decision/adoption.
The confidence items in the GGNPS include how confident nurses are about knowing
what family history information is required to evaluate a patient's susceptibility to common
diseases. Additional items include nurses' confidence about discussing how family history
information affects screening intervals, deciding which patients would benefit from referrals to
genetic specialists, and facilitating referrals. Items also concern confidence in the ability to
access reliable and current information about genetics/genomics. Lastly, the GGNPS evaluates
Social Systems
Competency
/Knowledge
Attitudes/Receptivity
Decision/Adoption
Confidence

how confident nurses are about providing patients with information about the risks, benefits, and
limitations of genetic testing for common diseases.
Calzone and colleagues (2012) reported that only 24% of nurses (n =38/159) were
somewhat or very confident in deciding what family history information is needed to assess
susceptibility to common diseases. Furthermore, Metcalfe and colleagues (2009) reported that,
among hospice nurses, only 3% (n = 3/100) of participants were confident enough to teach
clients and only 20% (n = 20/100) were very confident about explaining how a gene causing
Duchenne Muscular Dystrophy is inherited. These findings are further confirmed in other
nursing specialties outside of hospice care. Andrews and colleagues (2014) noted that many
nurses, in a variety of specialties, lack confidence and this may adversely affect adoption of
genetics/genomics.
Competency/knowledge and confidence. If nurses do not feel confident about their
knowledge, they may not form a positive attitude and thus not provide education about
genetics/genomics, collect family history information, or consider referrals to genetic specialists.
This is true in contexts other than genetics/genomics. In the previously mentioned brain rest
study by Cook and colleagues (2013), researchers studied the effect of an educational
intervention on the confidence of nurses caring for patients with mTBI. The educational
intervention increased nurses' knowledge of symptom assessment and brain test guidelines. It
also increased nurses' confidence in interpreting symptom assessment scores (χ² = 18.05, p <
.001) and providing discharge instructions to patients and family members (χ² = 15.06, p < .001)
(Cook et al., 2013). However, though the educational intervention increased both the nurses’
knowledge and their confidence the authors did not evaluate the effect of knowledge on
confidence, a key relation in the present study.

Silva and colleagues (2016) did take that step. In a non-genetics/genomics study,
researchers evaluated the effect of knowledge on confidence. This effect was measured via an
educational program, about suicide risk assessment and management, on participants' confidence
and level of understanding. The study included 2,843 participants consisting of nurses,
physicians, case managers, administrators, and support staff. Applied Suicide Intervention Skills
Training (ASIST) is a two-day (14-hour total) workshop in which learners are taught to identify
individuals at risk of suicide and how to respond in a way that promotes safety and connects the
individual to community resources. Participants who completed the educational training had
statistically significantly higher confidence in their ability to assess clients and conduct
interventions than participants who did not receive the educational training F (1, 1333) = 298.21,
p < .001.
Confidence and decision/adoption. The previously mentioned systematic review of
nurses’ competence in genetics identified confidence as a main factor in adoption of
genetics/genomics into nursing practice (Skirton et al., 2012). Level of confidence was assessed
for such adoption activities as referring patients for genetic services, discussing genetic
testing/results, and completing a family history. For example, in a study about supporting
parents of children undergoing genetic investigation, Barr and McConkey (2006) reported that
nurses and midwives had low confidence in referring patients to genetic services; of the
participants, only 2.5% (n = 5/194) strongly agreed and 10.8% (n = 21/194) agreed that they felt
comfortable making a referral to a genetic counselor; 1.5% (n = 3/194) strongly agreed and 7.2%
(n = 14/194) agreed that they would feel comfortable discussing test results of pediatric patients
who underwent genetic testing.
Bottorff and colleagues (2005) reported similar findings in another reviewed study
assessing the knowledge, roles, and confidence regarding genetics/genomics among nurses in

Canada. Nurses (n = 975) reported consistently low confidence, ranging from approximately 1.5
– 2.5 on a 5 point Likert scale. Confidence was evaluated for activities reflective of adoption
such as gathering genetic information, providing referrals to genetic specialists, and obtaining
informed consent for release of genetic testing information. Both Barr and McConkey (2006)
and Bottorff and colleagues (2005) noted that decreased confidence may affect nurses’ use of
genetics/genomics in their clinical practice. Literature in this section explored the relation
between knowledge and confidence, confidence and attitudes/receptivity, and the resulting
indirect effect on adoption of innovations such as genetics/genomics. The following section will
explore the variable of ‘attitudes/receptivity.’
This is further supported by findings by Andrews and colleagues (2014), as they
evaluated characteristics of nurses who are more likely to adopt genetics/genomics into nursing
practice. Among a sample of 88 oncology and primary care nurses in the United Kingdom,
adopters were consistently more confident about collecting family history information (mw =
364.5, p < .001) than non-adopters. Researchers created a tool using questions from other
instruments and writing additional questions for this study. Questions from other instruments
were selected based on theoretical underpinning and relevance to this current study. New
questions were evaluated by content experts. The instrument was piloted with a sample of 14
oncology and primary care nurses, but no validity or reliability testing was reported.
Attitudes/Receptivity
Figure 5
Variables affecting Attitudes/Receptivity in the adapted model.

According to Rogers (2003), receptivity is the formation of a relatively enduring
“favorable or unfavorable attitude towards an innovation” (p. 169). Calzone and colleagues
(2012) further define attitudes/receptivity as the perception of advantages of genetics/genomics
as compared to previously used techniques. Therefore, attitudes/receptivity may favorably affect
adoption of an innovation if it is perceived as more advantageous than current clinical practice.
The GGNPS evaluates attitudes/receptivity, including the perceived importance of
becoming more educated about the genetics of common diseases. Calzone and colleagues (2013)
found that the majority of nurses felt that it was very important (67.5%; n = 410/607) or
somewhat important (26.7%; n = 162/607) for nurses to be more educated about the genomics of
common disease. In a previously discussed study, Carroll and colleagues (2009) report that,
when members of a small multidisciplinary workshop were asked about their attitudes toward
genetics/genomics, 95% (n = 20/21) reported that they perceived the content as important.
Likewise, Coleman and colleagues (2014) reported that 79% (n = 301/383) of participants felt it
was ‘very important’ for nurses to be more educated about genetics/genomics. This study also
used the GGNPS but included a diverse sample of nurses (Black/African American 33%, Asian
43%, Hispanic/Latino 18%, White 8%, American Indian 1%, Native Hawaiian/Pacific Islander
3%, and Other 12%), while many nursing studies underrepresent minorities. Overall, both of
these studies consistently reported that nurses had a positive attitude concerning the importance
of genetics/genomics to nursing practice.
Social Systems
Comp
etency
/Knowledge
Attitudes/Receptivity
Decision/Adoption
Confidence

The GGNPS also evaluates nurses’ perceptions of the potential advantages and
disadvantages of using genetics and genomics to support treatment decisions, improve service to
patients, and promote patient adherence to clinical recommendations. The attitudes section of the
GGNPS also evaluates nurses’ perceptions of the clinical advantages of using genetics/genomics.
An example of a major clinical advantage of genetics/genomics is its use in treatment selection to
promote effectiveness and decrease risks of adverse events. Evaluating the relation between
genetics/genomics and medication safety, Kelly and colleagues (2012) published case reports of
two deaths and one event of respiratory depression in children aged 3 to 5 years. Though all
three children received appropriate doses of codeine after tonsillectomy and/or adenoidectomy,
genetic variation resulted in ultra-rapid metabolism of codeine into morphine increasing the risk
for toxicity and death. Patients’ postmortem morphine levels were significantly higher than
therapeutic doses. In response to this information and following additional investigation, the
FDA (2017) issued an updated safety announcement indicating that codeine and tramadol should
not be administered to children under 12 years of age.
Research about the safety of codeine administration demonstrates the clinical advantages
of genetics/genomics to nursing practice and the following research by Metcalfe and colleagues
(2009) illustrates how nurses’ attitudes about such advantages can change. Researchers initially
reported that 43% (n = 43/100) of nurses felt that integrating genetics into hospice care was of
‘little importance’. However, as they progressed through reading the scenarios concerning
applications of genetics in hospice care, two thirds, up to 99%, rated genetics as ‘very important’
or ‘essential’ to palliative care (Metcalfe et al., 2009). Thus, knowledge changed their attitudes
towards advantages, to patients, of using genetics/genomics in their practice.
The GGNPS also evaluates attitudes towards the perceived disadvantages for nurses of
using genetics and genomics, such as a lack of time, reimbursement difficulties, and/or the need

to obtain a new skill set. Inadequate time to complete a high workload is a frequently reported
stressor among nurses. Tourangeau, Thomson, Cummings and Cranley (2013) reported that the
reasons for nurses leaving in-patient jobs included inadequate staffing (68.8%, n = 2718/3950),
unmanageable workload (62.1%, n = 2454/3950), and “inadequate time to do job well” (43.8%, n
= 1730/3950). Correspondingly, nurses report inadequate time as a major barrier to collecting
family history information, further demonstrating that high workload and inadequate time are
perceived disadvantages of genetics/genomics (Sussner, Jandorf, & Valdimarsdottir, 2011).
In a non-genetic/genomic context, but in a similar vein, a qualitative study by Lee (2004)
also highlighted time pressures perceived by nurses. This study used Rogers’ (2003) DOI model
to evaluate nurses’ perceptions of the innovation of computerized care systems. Interviews were
obtained from 12 nurses working in three respiratory intensive care units. Time shortage was
identified as a theme. Additional time required to use the computerized system was a stressor
that negatively affected nurses’ attitudes toward the innovation. They reported the perception
that management valued documentation more than patient outcomes.
Finally, the GGNPS evaluates nurses’ perceived disadvantages for patients. A potential
disadvantage is that receiving genetic testing results may be anxiety-provoking for patients. A
meta-analysis, by Hamilton, Lobel, and Moyer (2009), evaluated anxiety and distress related to
BRCA1/2 mutation testing. Twenty studies, totaling 2,171 participants (95.2% female), were
included. There were statistically significant differences in anxiety reported by carriers,
noncarriers, and individuals with inconclusive results after a short period of time (mixed effects
Q (2) = 22.41, p < .001); but no statistically significant difference in anxiety after a moderate
period of time (mixed effects Q (2) = 2.47, p =.29) (Hamilton et al., 2009). Patients may need
additional support and counseling in the period directly following genetic testing when their
anxiety may be elevated. Nurses can provide information about the tests results, as well as

limitations of currently available testing, and facilitate referrals, if warranted. In addition, nurses’
attitudes/receptivity about genetics/genomics may be affected by patient experiences of anxiety
or distress upon receiving genetic testing results.
An additional potential disadvantage of genetics/genomics for patients is loss of privacy
and fear of discrimination. A qualitative review of literature on the adoption of online therapy
among psychologists identified patient privacy and confidentiality concerns as potential barriers
to adoption of and attitudes toward online therapy by psychologists (Lovejoy, Demireva,
Grayson, & McNamara, 2009). These concerns parallel concerns about discrimination based on
genetic information among patients. Online services present challenges of safe record keeping
and HIPAA compliance. The use of passwords can provide security, but passwords may be
shared or intercepted by others. The researchers stressed reporting to clients that online sessions
have limits of confidentiality and there are associated risks and benefits. In addition, providers
need to obtain information prior to initiating therapy (such as name and address) in case of an
emergency. Concerns about loss of privacy and fear of discrimination by patients were a barrier
to adoption of the innovation by the health care providers. Privacy concerns by patients may
affect nurses’ attitudes towards adoption of genetics/genomics. Educating nurses about the
Genetic Information Nondiscrimination Act (GINA) of 2008 can correct misconceptions about
lack of privacy and address the fear of discrimination.
Attitudes/receptivity and decision/adoption. Nurses’ attitudes towards
genetics/genomics are hypothesized to directly affect its adoption into one’s clinical practice. It
was noted that nurses are time stressed and do not have time to do their jobs properly and
perceive this as a deterrent to aspects of their practice that are not mandated by administration
(Tourangeau et al., 2013). Jenkins and Calzone (2007) reported that evaluation of a family
history by a registered nurse is not reimbursed. Nurses have many time-sensitive roles and

responsibilities required for continued employment in an organization. If medications are not
administered within the required time period, many health care documentation systems require
written explanations about why this occurred. Some health care institutions also monitor call
bell response time (Roszell, Jones, & Lynn, 2009). Unlike medication administration and call
bell response times, employers do not currently monitor collection of family history information.
In addition, nurses often do not know how to use the information after it is obtained or where to
document it in the patient’s chart. This may contribute to Calzone and colleagues (2014)
findings that, although nurses recognized the importance of genetics and genomics in clinical
practice, actual adoption of this innovation is low.
Confidence and attitudes/receptivity. In the present study, it is hypothesized that
confidence has a direct effect on one’s attitude/receptivity. Calzone and colleagues (2013) noted
that only 27.5% of surveyed nurses reported being confident or very confident about choosing
what family history information was needed to assess genetic susceptibility to common diseases.
Given such low confidence, it was expected that the same surveyed nurses would report an
unfavorable attitude towards use of genetics/genomics. Interestingly, 94.2% of surveyed nurses
felt that it was very important or somewhat important for nurses to become more educated about
genomics of common disease, thus demonstrating a positive attitude.
While this study seems to indicate that low confidence may not directly influence nurses’
positive attitudes/receptivity regarding genetics/genomics, nurses’ attitudes towards the
importance of nurses learning more about genetics/genomics are only one piece of the GGNPS
attitudes section (Calzone et al., 2013). The other attitudes items assess nurses’ perceptions of
advantages and disadvantages to both themselves and their patients. Furthermore, as detailed
below, knowledge and social systems also affect nurses’ attitudes. It is thus likely that, one or
both of these factors may have a stronger effect on attitudes than does confidence alone.

Concerning the influence of knowledge Metcalfe and colleagues (2009) evaluated the
confidence and attitudes of hospice nurses regarding the use of genetics in their clinical roles. As
previously noted, initially the attitude of 43% (n = 43/100) of the nurses was that integrating
genetics into hospice care was of ‘little importance’ and only 3% (n = 3/100) were confident
enough to teach clients. However, after reading scenarios about applications of genetics in
hospice care, two thirds, up to 99%, rated genetics as ‘very important’ or ‘essential’ (Metcalfe et
al., 2009). Perhaps it was not just confidence that affected attitudes but also the knowledge
gained through exposure to relevant clinical scenarios.
Social systems and attitudes/receptivity. Regarding social systems’ influence on
nurses’ attitudes/receptivity about genetics/genomics the most frequently reported stressors
among nurses include inadequate time, inadequate resources, an unsupportive organization,
inadequate staffing, and a poor work environment (Tourangeau et al., 2013). The addition of
genetic/genomic responsibilities to nursing practice results in even more time pressure (Sussner
et al., 2011) and can negatively affect their attitude towards these responsibilities.
Genetics/genomics may create additional time pressure because nurses frequently report
inadequate time to complete their current workload and would have additional responsibilities
such as collection of family history information, patient education, and facilitating referrals to
genetic specialists.
Likewise, the support of supervisors or managers likely affects nurses’ attitudes about
genetics/genomics. In the previously discussed study by Calzone and colleagues (2014), only
25.3% (n = 1,342/5,314) of participants reported they believed their senior staff members
considered genetics as an important part of the participants’ role. In addition, 45.5% (n =
2,430/5,343) reported they could not attend a genetics/genomics course during work hours.

This may be due to the fact that, registered nurses and health care organizations are not
reimbursed if nurses collect or evaluate family history data (Jenkins & Calzone, 2007). Nor is
their reimbursement jeopardized by nurses’ failure to collect and evaluate this data. Beginning in
2012, the Center for Medicare and Medicaid Services began using the Hospital Consumer
Assessment of Healthcare Providers and Systems (HCAHPS) patient satisfaction survey to
determine reimbursement of 1% of diagnosis related group (DRG) payments, or $850 million
dollars (Zusman, 2012). This number is likely to increase in the coming years as private insurers
adopt similar strategies. This creates a social pressure among hospital administrators, and
therefore nurses, to prioritize care that is reflected on HCAHPS, such as prompt call bell
response time. By contrast, collecting family history information and facilitating referrals to
genetic specialists are not items evaluated on HCAHPS or reimbursed for registered nurses.
Thus, pressure to complete many required responsibilities, lack of supervisory support, and a
lack of reimbursement create potential social systems-related pressures that can influence nurses’
attitudes towards genetics/genomics use in their own practice. Reimbursement affects not only
nurses’ attitudes towards genetics/genomics, but also the affect social systems may have on
adoption. Health care organizations may prioritize care that increases reimbursement to meet
budgetary needs and increase revenue (Trinkoff et al., 2011). However, it is important for health
care organizations to consider value-based care. This health care model focuses on positive
patient outcomes per dollar spent; to contain costs (by decreasing unnecessary tests and
procedures) and prioritize effective patient care. While hospitals may feel pressured to increase
reimbursement, ultimate responsibilities of health care institutions are to use available resources
(such as genetics/genomics) to improve patient outcomes.
Conclusion

Genetics/genomics is used in all aspects of clinical care; because it is so widely used in
health care, adoption of genetics/genomics is required to provide safe, evidence-based, and
competent nursing care. A valid and reliable instrument evaluating nurses’
competency/knowledge, confidence, attitudes/receptivity, decision/adoption of this content, as
well as the effect of social systems, can be used to identify gaps in knowledge, deficits in
confidence, nurses’ attitudes and perceptions of the of the use genetics/genomics in clinical
practice, potential barriers, and ultimately adoption of the content into nursing practice. This
information can be used to create continuing education initiatives, changes in curricula, clinical
competencies, and/or policy initiatives.
Chapter III
The Method
The purpose of this study was to evaluate the Genetics and Genomics in Nursing Practice
Survey (GGNPS) instrument for construct, content, and face validity. This chapter presents the
study method and is organized into five sections: (a) design, (b) sample, (c) data collection
procedures, (d) instrument, and (e) data analysis.
Design
In this secondary analysis of data, a content validity ratio was calculated from a content
validity index. Eight nursing experts were selected based on current publications and clinical
expertise. Some of the experts were clinicians providing care to patients with genetic conditions,
others researchers with expertise in genetics/genomics, and others experts in ethical, legal, and
social implications (ELSI) of genetics. Content validity evaluation informed this analysis via
feedback from nursing experts about each individual item in the GGNPS, as well as via a
comprehensive CVI score for the overall instrument.

A Confirmatory Factor Analysis (CFA) was conducted to test the fit of a factor model,
based on Rogers’ DOI model, to data from GGNPS surveys administered to a nationwide sample
of Registered Nurses (RNs) (Calzone et al., 2016). A CFA was used because it evaluated the fit
between a theory-proposed model and empirical data (Comrey & Lee, 2013). The latent
variables were created based on mapping the GGNPS items to the DOI model. The latent
variables used in this analysis were identified using conceptual and operational definitions
designated by Calzone and colleagues (2012), who based the variables and construction of the
GGNPS on Rogers’ DOI model (Rogers, 2003).
Construct validity was also analyzed via structural equation models (SEMs). The SEMs
tested model fit and the relations between the factors described in Rogers’ DOI model. The
ultimate goal of the SEMs was to evaluate how well the proposed model predicted adoption of
genetics/genomics into nursing practice.
Following the secondary data analysis, new participants were recruited to evaluate face
validity. Face validity was assessed via feedback on the GGNPS from seven currently practicing
RNs. Participants included nurses with one year or more clinical experience, working in a
variety of practice areas (acute and community settings). Clinical competence as an RN was
determined by current employment and duration of nursing experience (one year or greater). To
prevent sampling bias, nurses were recruited from a variety of clinical backgrounds. Participants
were practicing RNs with an associate, bachelors, master’s, or doctoral degrees. Participants had
a variety of clinical experience, ranging from 2 to 31 years of nursing practice. Face validity
informed the analysis by providing insight into how the instrument is understood and interpreted
by participants.

Sample
Calzone and colleagues (2014) collected GGNPS data from 7,798 RNs from 17 states,
representing all regions of the U.S. At the time of the survey, the nurses were employed at one of
23 Magnet® Recognition Program hospitals. Institutions included acute care centers, three
children’s hospitals, a Veterans Administration, one rural hospital, one psychiatric hospital, and
one cancer center. Nurses participated in a one-year study to evaluate nurses’
competency/knowledge, confidence, attitudes/receptivity, and the effects of social systems on
their adoption of genetics/genomics into their clinical practice. Data were collected at baseline
and following a one-year competency integration initiative. The baseline data was used for this
study. Baseline data was selected because it is most likely to reflect competency/knowledge,
confidence, attitudes/receptivity, effect of social systems, and adoption of genetics/genomics
among RNs within the U.S., as opposed to RNs who participated in an initiative to incorporate
genetics/genomics into their clinical practice. Eligibility criteria for the sample included being a
RN currently employed at the health care center at the time of survey administration. RNs of all
academic backgrounds were eligible to participate.
Data Collection Procedures
Institutional review board approval for this study was sought from the College of Staten
Island (CUNY). Exempt status was sought because data were not collected with identifying
information. Research using pre-existing data is exempt from institutional review board
evaluation if information is recorded in a way that participants cannot be directly or indirectly
identified. After obtaining exemption, the investigator downloaded the dataset onto a
passwordprotected computer; because there is no direct involvement with human subjects and
will be conducted on previously collected and de-identified data, no harm to human subjects is
anticipated.

Calzone and colleagues (2014) originally collected the data following approval from the
Institutional Review Board (IRB) of West Virginia University (WVU). A reliance agreement was
also established between WVU and the Office of Human Subjects Research at the National
Institutes of Health (NIH); some institutions relied on the WVU-IRB approval, others required
additional IRB review by their institutions.
The GGNPS was administered at each health care institution between July and October
2012 as part of a multi-institution project called Method for Introducing a New Competency into
Nursing Practice (MINC) (Calzone et al., 2014). The project included 23 hospitals; baseline data
was collected from 7,798 RNs. Response rates varied from 17% to 63%. The survey was open
for completion for 28 days. Recruitment was conducted via email notification; however,
institutions could utilize additional recruitment strategies such as advertising, supervisor
encouragement, intranet posting, and incentives in accordance with local IRB approval. The
baseline data collected at the initiation of the MINC project was used for the statistical analysis in
this study.
Instrument
Origins. The GGNPS was derived from an instrument used to evaluate components of
the DOI model: attitudes, knowledge, competency, receptivity, confidence, and adoption of
genetics/genomics by family physicians (FP’s), as well as the effect of social systems (Jenkins et
al., 2010). It was developed by a team consisting of FPs, survey designers, a behavioral scientist,
and experts in genetics/genomics. Content validity for the FP instrument was evaluated by
content experts. A confirmatory factor analysis (CFA) was done on data from the pilot study,
individual factor loadings were not reported in the article.
Construct validation was conducted using structural equation modeling (SEM). SEM was
used to evaluate whether the items in the instrument aligned with the DOI domains and evaluate

the paths among the variables. The results of the SEM for the FP instrument included: Tucker
Lewis index (TLI=.92, > .9), root mean square error of approximation (RMSEA=.039;
90% confidence interval, < .08), and standardized root mean square residual (SRMR=.056, < .1)
(Jenkins et al., 2010). Jenkins and colleagues (2010) report that the findings indicate the
instrument is aligned with the domains of the DOI.
While the standardized path weights were statistically significant (p < 0.001), Jenkins and
colleagues (2010) noted two pathways leading to adoption of genomic-related innovations, as
opposed to one pathway as predicted by Rogers’ DOI model. SEM was used to evaluate
pathways that influenced FP’s adoption of genomic-related innovations. In pathway 1, adoption
of genetics/genomics into clinical practice by FP’s was associated with increased comfort with
using genetic information. In pathway 2, adoption was associated with perceived relevance of
family history and genetics of common diseases information to clinical practice.
GGNPS development. The FP instrument was adjusted for nursing practice. To do this,
Calzone and colleagues (2012) consulted with nursing and genomic nursing experts. The items
were evaluated for nursing scope of practice, consistency with genomic competencies for nurses,
and for content validity. The content experts reviewed the proposed instrument and provided
feedback and suggested changes. Though the provided feedback was not published, content
experts agreed with edits made to the FP instrument, revising it for nursing scope of practice.
Edits included changing items about referring clients to genetic/genomic services to “facilitating
referrals” and medication administration as opposed to prescribing medications.
The GGNPS was first pilot tested for usability by a convenience sample of five nurses
and tested again using a larger sample (Calzone et al., 2012). A second pilot test was conducted
on a larger sample of 239 RNs employed at the NIH, response rate was 28%. The GGNPS was
amended following pilot testing. Amendments were based on feedback, follow-up review by

experts, and recommendations from pilot test participants. Amendments included the removal of
questions that expert reviewers considered unclear and addition of two questions about
knowledge of genetics of common diseases from the Genetic Variation Knowledge Assessment
Index (GKAI).
GKAI. The GKAI is an instrument evaluating health care professionals’ knowledge of
genetic variation and race. The GKAI was evaluated for validity via confirmatory and
exploratory factor analysis, expert advisory panels, and focus groups (Bonham, Sellers, &
Woolford, 2014). Two questions pertaining to genetic/genomic knowledge were added to the
GGNPS with permission from the developers and authors.
Reliability testing. Reliability testing was conducted on data from two institutions
participating in the MINC study (Calzone et al., 2016). The MINC study included a baseline
assessment and an assessment at the completion of the one-year educational intervention.
Reliability testing was conducted following the educational intervention; those participants
completed the instrument twice to assess for test-retest reliability. At Time 1, the GGNPS was
available electronically for completion for 28 days. One week later the survey was opened for 14
days for Time 2 (retest). Participants were provided a personal study number to match responses
for both time periods. If responders did not have the same number for Times 1 and 2, had a
missing number, or a duplicate number with another participant, then they were excluded from
the study. A personal study number was used in place of identifying data to promote
confidentiality. A total of 993 RNs completed the GGNPS at Time 1 and 564 at Time 2.
However, after excluding responses that were missing a personal study number, used a duplicate
number, or had all data missing for Times 1 or 2, 232 responses were used for analysis.
During reliability testing, Likert scale items with five or more options performed poorly
and the questions were amended, by shortening the scale, to provide more accurate results in

future testing. Moderate agreement was classified as a Kappa of 0.41-0.60 (Landis & Koch,
1977). Moderate agreement was achieved in 39% (n = 36/95) of instrument items. The mean
agreement across all items in the instrument was a Kappa of 0.407 (range 0.150-1.000) (Calzone
et al., 2016).
‘Select-all-that-apply’ items performed the poorest, mean K=0.308 (range 0.165-0.432)
for questions pertaining to attitude/receptivity and mean K=0.262 (range 0.150-0.394) for
questions pertaining to self-assessment of ability to discuss genetics of common diseases with
clients (Calzone et al., 2016). Among the Likert scale items, questions with 7 response options
performed poorly, mean Kw=0.324 (range 0.216-0.375), while Likert scale items with 4 or 3
response options performed better (Calzone et al., 2016). Of the two items that were revised, one
was in the Competency/knowledge domain and one in Attitudes/Receptivity.
The version of the GGNPS used for this study did not include amendments made
following reliability testing, because reliability testing was completed after baseline data was
collected in the MINC study. The baseline data sample was a robust nation-wide sample well
suited for statistical modeling. The analysis considered how amendments to the GGNPS,
following reliability testing, may have affected the statistical analysis. Future research will
include redistributing the revised instrument and comparing the SEM results.
Content. The GGNPS includes nominal (such as true/false and yes/ no questions) and
ordinal questions. The GGNPS domains include decision/adoption, competency/knowledge,
attitudes/receptivity, confidence, and the effects of social systems. The decision/adoption domain
includes four questions about how often, in the past three months, have participants collected a
complete family history, cared for a patient who initiated a discussion about genetics/genomics,
facilitated a referral for genetic services, and used family history information to facilitate clinical
decisions or patient recommendations. Collection of family history information is used as a

measure of adoption because it is not dependent on technology or financial resources. The
competency/knowledge domain includes 20 questions asking participants to agree/disagree or
mark “don’t know” for statements about how family history is collected, such as which relatives
are included. The competency/knowledge domain also includes questions about genetic risk
associated with breast cancer, colon cancer, coronary heart disease, diabetes, and ovarian cancer.
Additional questions include which information is collected when patients indicate a disorder in
the family (age of diagnosis, relation to the patient, race/ethnicity, age of death from condition,
information from both maternal/paternal lineages), as well as questions about DNA structure,
gene variants associated with diabetes/heart disease, and awareness of the Essential
Competencies and Curricula Guidelines. The final questions ask participants to evaluate their
understanding of genetics of common disease through self-report. Thus, questions in the
competency/knowledge domains evaluate both self-reported knowledge and objectively test
nurses’ knowledge of genetics/genomics, providing both subjective and objective measures. The
attitudes/receptivity domain includes ten subjective questions about the potential advantages and
disadvantages of integrating genetics/genomics into clinical practice, the perceived importance of
becoming more educated about the genetics/genomics of common diseases, and taking a family
history as a component of nursing care. The confidence domain includes eight questions about
nurses’ self-reported confidence regarding what family history information is needed to evaluate
susceptibility to common diseases, discussing how family history affects screening for diseases,
which patients may benefit from referrals for genetic counseling and testing, providing patients
with information regarding risks/benefits of genetic testing, and facilitating referrals for genetic
services. The social system domain includes five questions about whether participants feel that
senior staff members view genetics/genomics as an important part of a nurse’s role as well as
their own role. Additional questions ask if participants would attend genetics/genomics classes

on their own time, could take a class during work hours, and if they intend to learn more about
genetics.
In scoring the GGNPS, items from the confidence, attitudes/receptivity, social system,
and adoption domains were analyzed independently and not combined to form an overall score.
The twelve competency/knowledge items were combined to form a knowledge score, making
knowledge a continuous variable (see Appendix B). Responses to the twelve-
competency/knowledge items were marked as correct (1) or incorrect (0). If participants
responded “don’t know” that was also marked as incorrect (0), the number of correct answers
was added, generating a score from 0 to 12. Calculation of a total competency/knowledge score
was restricted to surveys where all 12 questions were answered.
Data Analysis
Data was downloaded into Microsoft Excel 2010 spread sheets. It was analyzed using
Mplus version 7.3 and R version 3.1.2. Data was analyzed in three steps. GGNPS items are
nominal, ordinal, and continuous variables. As a result, finite mixture models were used to
evaluate the heterogeneity and underlying distribution among the latent variables. The data
analysis included attempting to measure the CFA of a model comprised of Rogers’ DOI factors:
competency/knowledge, confidence, attitudes/receptivity, social systems, and decision/adoption.
SEMs were conducted to evaluate the overall model fit and the relation between the
factors; relations were evaluated based on Rogers’ (2003) DOI model. Chi-square fit tests were
used to determine the fit of the proposed path models to the data and to compare the relative fit
of the models with each other (Hoyle, 1995). Consideration was given to the limitation of the
chi-square test with a large sample size; statistical tests such as RMSEA, BIC, and CFI were also
evaluated (Browne & Cudeck, 1993).

Content validity was calculated using a content validity ratio. Eight experts in nursing
and genetics/genomics were sent a content validity index derived from the GGNPS. Experts
were defined as individuals who have current employment, experience, and evidence of
scholarship in both nursing and genetics/genomics. Furthermore, experts with backgrounds in
genetic/genomic research, education, and clinical practice (as opposed to solely bench science)
were selected, because the GGNPS is a tool for nurses to apply genetics/genomics to their
clinical practice. The content validity index was created from each item in the GGNPS with the
definition of each domain and corresponding items provided for the content experts. A relevance
table with four categories (ranging from ‘very relevant’ to ‘not relevant’) was used to score each
item (Lawshe, 1975). The content validity ratio was calculated using Lawshe’s formula:
CVR = [Ne – (N/2)]/ (N/2)
In this formula Ne was the number of panelists who classified the item as ‘very relevant’ or
‘relevant’ and N is the total number of content experts. Revisions, based on the CVR and the
overall CVI score, were proposed.
An exploratory factor analysis (EFA) was conducted because the CFA was unable to
converge on a stable set of parameter estimates. The items that were hypothesized to make up
the variables of competency/knowledge, attitudes/receptivity, confidence, decision/adoption, and
social systems could not be grouped as hypothesized when the CFA analysis was conducted.
Iterative maximum likelihood calculations were unable to fit the proposed variables to the data.
A follow-up EFA analysis indicated that this may be due to items being related to variables
different than those that were originally hypothesized. In addition, some items may have
grouped together due to similar formatting (e.g. confidence items).

In an EFA, factor loadings are derived from relations among the data; the data-driven
EFA compliments the theory-driven CFA, based on work by Calzone and colleagues (2012) and
Rogers’ (2003) DOI theory. The EFA provided additional insight into which items comprised the
variables of competency/knowledge, attitudes/receptivity, confidence, socials systems, and
decision/adoption.

Chapter IV
Results
The purpose of this study was to test the content, face and construct validity of the
Genetics and Genomics Nursing Practice Survey (GGNPS) (Calzone et al., 2012). A content
validity ratio (CVR) was first calculated on data from seven content validity experts. Then face
validity was evaluated via feedback from seven currently practicing RNs. Finally, construct
validity was evaluated in two ways using existing data from GGNPS surveys administered to a
nationwide sample of RNs (Calzone et al., 2016): 1) a Confirmatory Factor Analysis (CFA)
tested the fit of a factor model, based on Rogers’ DOI model, to these data; 2) A series of
structural equation models tested the fit between hypothesized relations described in Rogers’
DOI model and these data. An Exploratory Factor Analysis (EFA) was conducted to gain insight
about why the CFA was unable to converge and to explore relations among the items in the
GGNPS to inform future analyses.
The GGNPS The GGNPS measures nurses’ competency/knowledge, attitudes/receptivity,
confidence, and decision/adoption of genetics and genomics, as well as the effects of social
systems on adoption. The format includes a mix of multiple-choice, dichotomous, and Likert-
scale questions. A knowledge score was calculated by totaling the number of correct responses
to the 12 knowledge items (knowledge scores range from 0 to 12). Cumulative scores were not
calculated for the attitudes/receptivity, confidence, social system, and decision/adoption
variables; this is because some items in those variables were responders’ subjective opinions
(e.g. “Please indicate whether you agree or disagree with the following statements”). The
instrument also includes demographic data.

Data Collection Results and Response Rates
This is a secondary analysis of data collected as baseline data (time 1) as part of Calzone
and colleagues’ (2014) yearlong intervention aimed at improving nurses’ capacity to integrate
genetics and genomics into their clinical practice. RNs from a total of 23 Magnet® designated
hospitals, across 17 states, participated in this study. In those 23 hospitals, RNs with any role (n
= 27,613) were eligible to participate. Response rates of eligible participants varied from 1763%
between hospitals. The GGNPS was administered between July and October 2012. It was open
for completion at each institution for 28 days. Institutions sent an email notification of the
survey availability and reminder emails as well as using additional recruitment strategies such as
advertising, intranet posting, and supervisor encouragement.
All participating hospitals reported similar barriers to completion, such as burden due to
time constraints of practicing nurses; 100% of the institutions were concerned with survey
burden and had conducted institution-wide nursing surveys in the past six months. A total of
7,842 responses were received. Of these, Calzone and colleagues (2014) excluded 12 non-RN
respondents and an additional 32 respondents who did not report hospital affiliation. This
resulted in 7,798 eligible respondents and an overall 28% response rate.
Missing Data
Of these 7,798, 8.71% ( n = 679) respondents left all items blank and were excluded,
leaving 7,119 respondents. Figure 6 contains a frequency distribution of the percentage of the
GGNPS participants completed (range 0-100%). Demographic items provide important
information about participants, such as clinical experience. The sample was first inspected for
respondents who answered most demographic items, but omitted some answers to study
variables. A ratio was calculated of demographic items answered to total items answered.
Individuals who had a z-score of +/-3 or greater were excluded (n = 3). These individuals
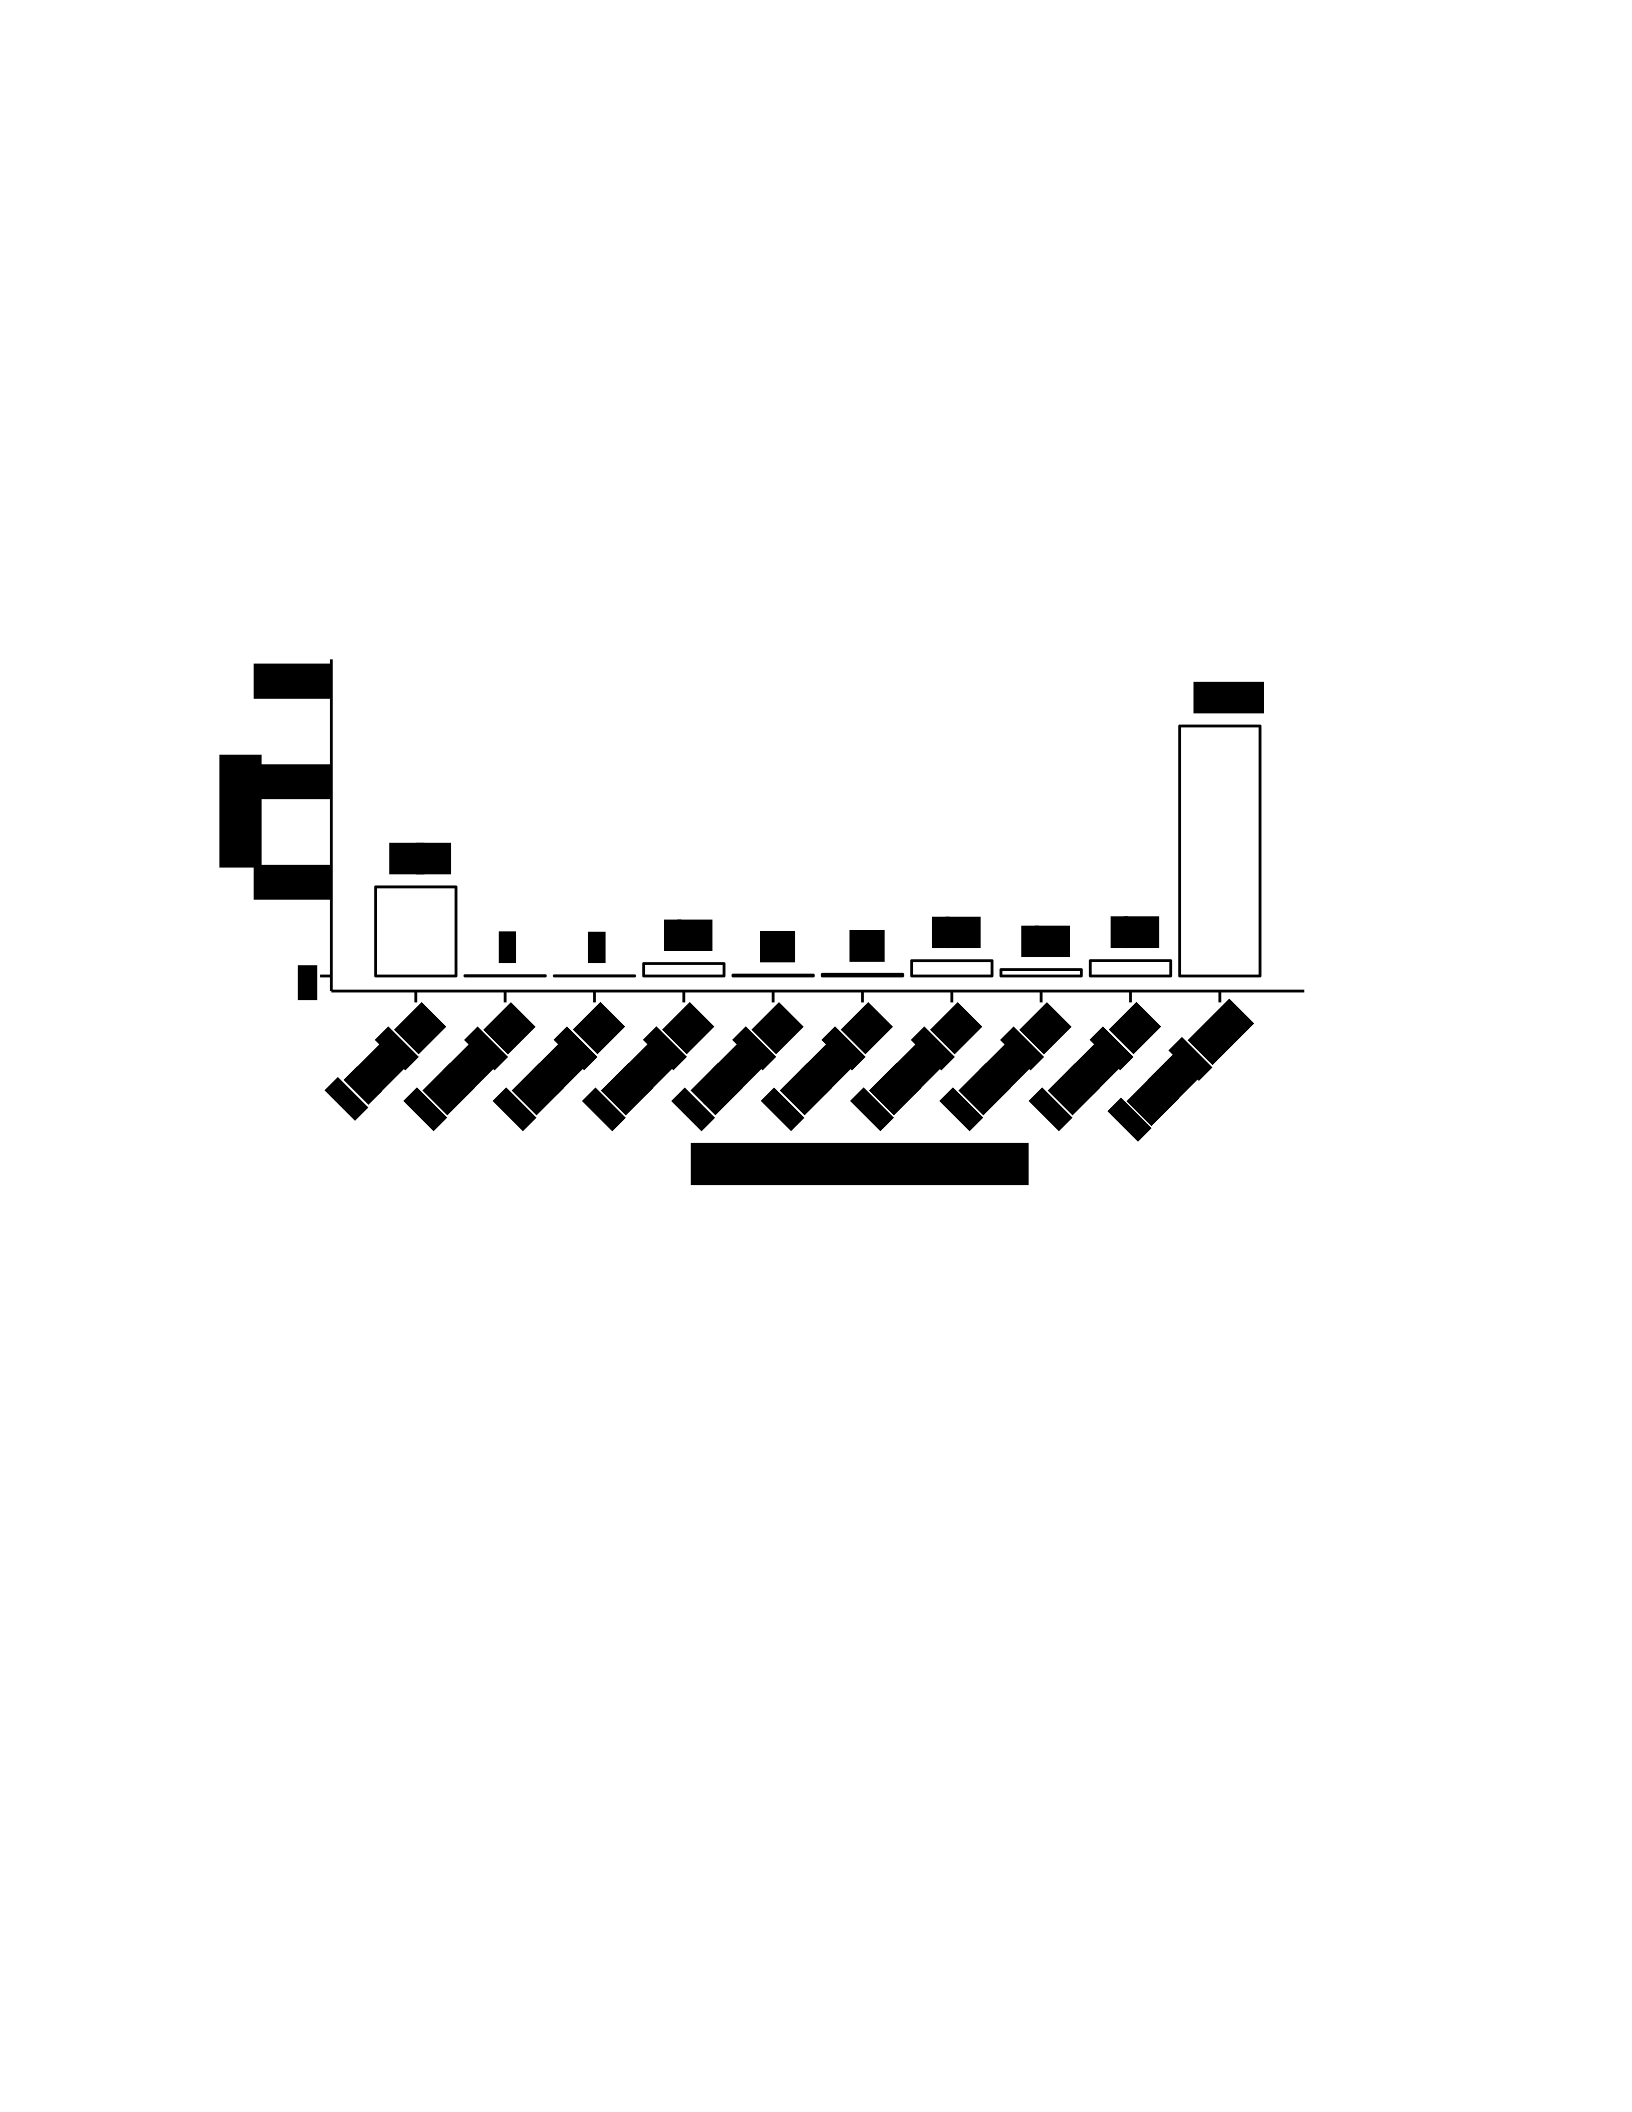
answered a majority of demographic items, without providing information pertinent to evaluation
of the study variables. This left 7,116 respondents.
Figure 6
Percent of GGNPS Completed by Participants.
When evaluating the relations between study variables, analyses may be affected if items
are answered mostly for one study variable, but not others. Thus, respondents who answered the
majority of items pertaining to one variable (e.g., social systems), but not to the other variables,
were removed. Ratios between complete data on individual variables versus the entire
instrument were calculated (see Table 1); individuals who had a z-score of +/-3 or greater were
excluded. Notably, excluded individuals answered the confidence and/or decision/adoption items
which were grouped in the beginning of the GGNPS. Thus, these individuals likely answered
items in the beginning, then left an increasing amount of items blank as they proceeded through
73
17
7
4
48
2
18
35
3
05
28
1
06
3
4974
0
2000
4000
6000
Percent Complete

the GGNPS. Seven individuals had a z-score of +/-3 in relation to both confidence and
decision/adoption as compared to the entire instrument.
Table 1 z-Scores +/- 3 for All
Variables.
Ratio
Number of Participants with z-Score +/- 3
Social Systems to total
GGNPS Complete
0
Competency/Knowledge to
total GGNPS Complete
1
Confidence to total GGNPS
Complete
127
Attitude/Receptivity to total
GGNPS Complete
0
Decision/Adoption to total
GGNPS Complete
134
Data from the remaining 6,861 respondents were then examined for missing data patterns.
Prior to evaluating whether data were missing at random (MAR) (Tabachnick, Fidell, &
Osterlind, 2001), normality tests were conducted to determine whether parametric or
nonparametric tests should be utilized to evaluate missing data. The Anderson-Darling and the
Cramer-von Mises (Razali, Wah, 2011) tests demonstrated statistically significant deviations (p <
.05) from a normal distribution. While this indicates that the data may not be normally
distributed, this is an expected result due to the large sample size (see Tables 2 and 3). Q-Q
plots, a graphical representation of normality, suggest that deviations from normality were small
and tended to occur near the tails of the distribution (see Appendices C.1-C.5); however, the
confidence and social system variables demonstrated truncated tails, implying range restriction.
Because the deviations of the data from normality appeared small, parametric tests were used to
evaluate whether data were MAR.

Table 2
Cramer-von Mises Normality Test.
Variable
Cramer-von Mises Normality Test Value
p-Value
Social Systems
18.577
p < .001
Competency/Knowledge
.89781
p < .001
Knowledge Score (0-12)
.06666
p = .3093
Confidence
6.5058
p < .001
Attitude/Receptivity
5.4833
p < .001
Decision/Adoption 2.4749 p < .001
Table 3
Anderson-Darling Normality Test.
Variable
Anderson-Darling Normality Test Value
p Value
Social Systems
118.31
p < .001
Competency/Knowledge
5.1671
p < .001
Knowledge Score (0-12)
.38739
p = .3877
Confidence
46.437
p < .001
Attitude/Receptivity
31.891
p < .001
Decision/Adoption 14.794 p < .001

Welch’s two-sample independent t-tests were then used to determine if data could be
considered MAR. That is, whether there was no statistically significant mean difference in one
variable (e.g., confidence) if an item in a different variable (e.g., decision/adoption) was
unanswered (see Appendix D). To evaluate this, marginal mean imputation was used to conduct
the t-tests; without imputation, the t-tests would provide information about the frequency of
missing data, as opposed to the relations between the missing items. Sidak family-wise error
correction was used to determine the family-wise α-values for multiple t-tests. Missingness on
decision/adoption items could not be considered to be MAR, while missingness on other
variables did appear to be MAR (see Appendix D). Because all data are not MAR, multiple
imputation, the most statistically robust method, was used to account for missing items
(Carpenter, Kenward, & Vansteelandt, 2006).
Multiple imputation replaces missing data with values imputed from the values of all
existing data for that individual given the values for that score that tend to co-occur with similar
values for other individuals. This process of imputation is conducted for all individuals and all
items; the resulting model is then re-analyzed and the process carried on iteratively. For this
analysis, multiple imputation was conducted using the Mice package in R, Version 3.2.3 (2013).
This package uses different models to estimate data for nominal, ordinal, and interval values; this
is an advantage because the GGNPS contains a variety of items including Likert-scales, “yes/no”
items, and a knowledge score. In addition, the Mice package imputes data beginning with the
variable that has the least amount of data missing, utilizing the most complete variables to fill in
data on less complete variables and thus using the maximal amount of information for each
imputation. Finally, the Mice package also uses random draws of data to mimic natural
variability in the sample.

Four imputations were conducted with 50 iterations for each imputation. The multiple
iterations allow the imputed data to try multiple variations until a “best-fit” scenario is found.
ANOVAs compared means of the four imputations. Results demonstrated that there were no
statistically significant differences between the imputations (see Table 4). This indicates that
with four different imputations the data sets were consistently similar, demonstrating increased
likelihood that the data was imputed based on the parameters of the collected data. Table 4
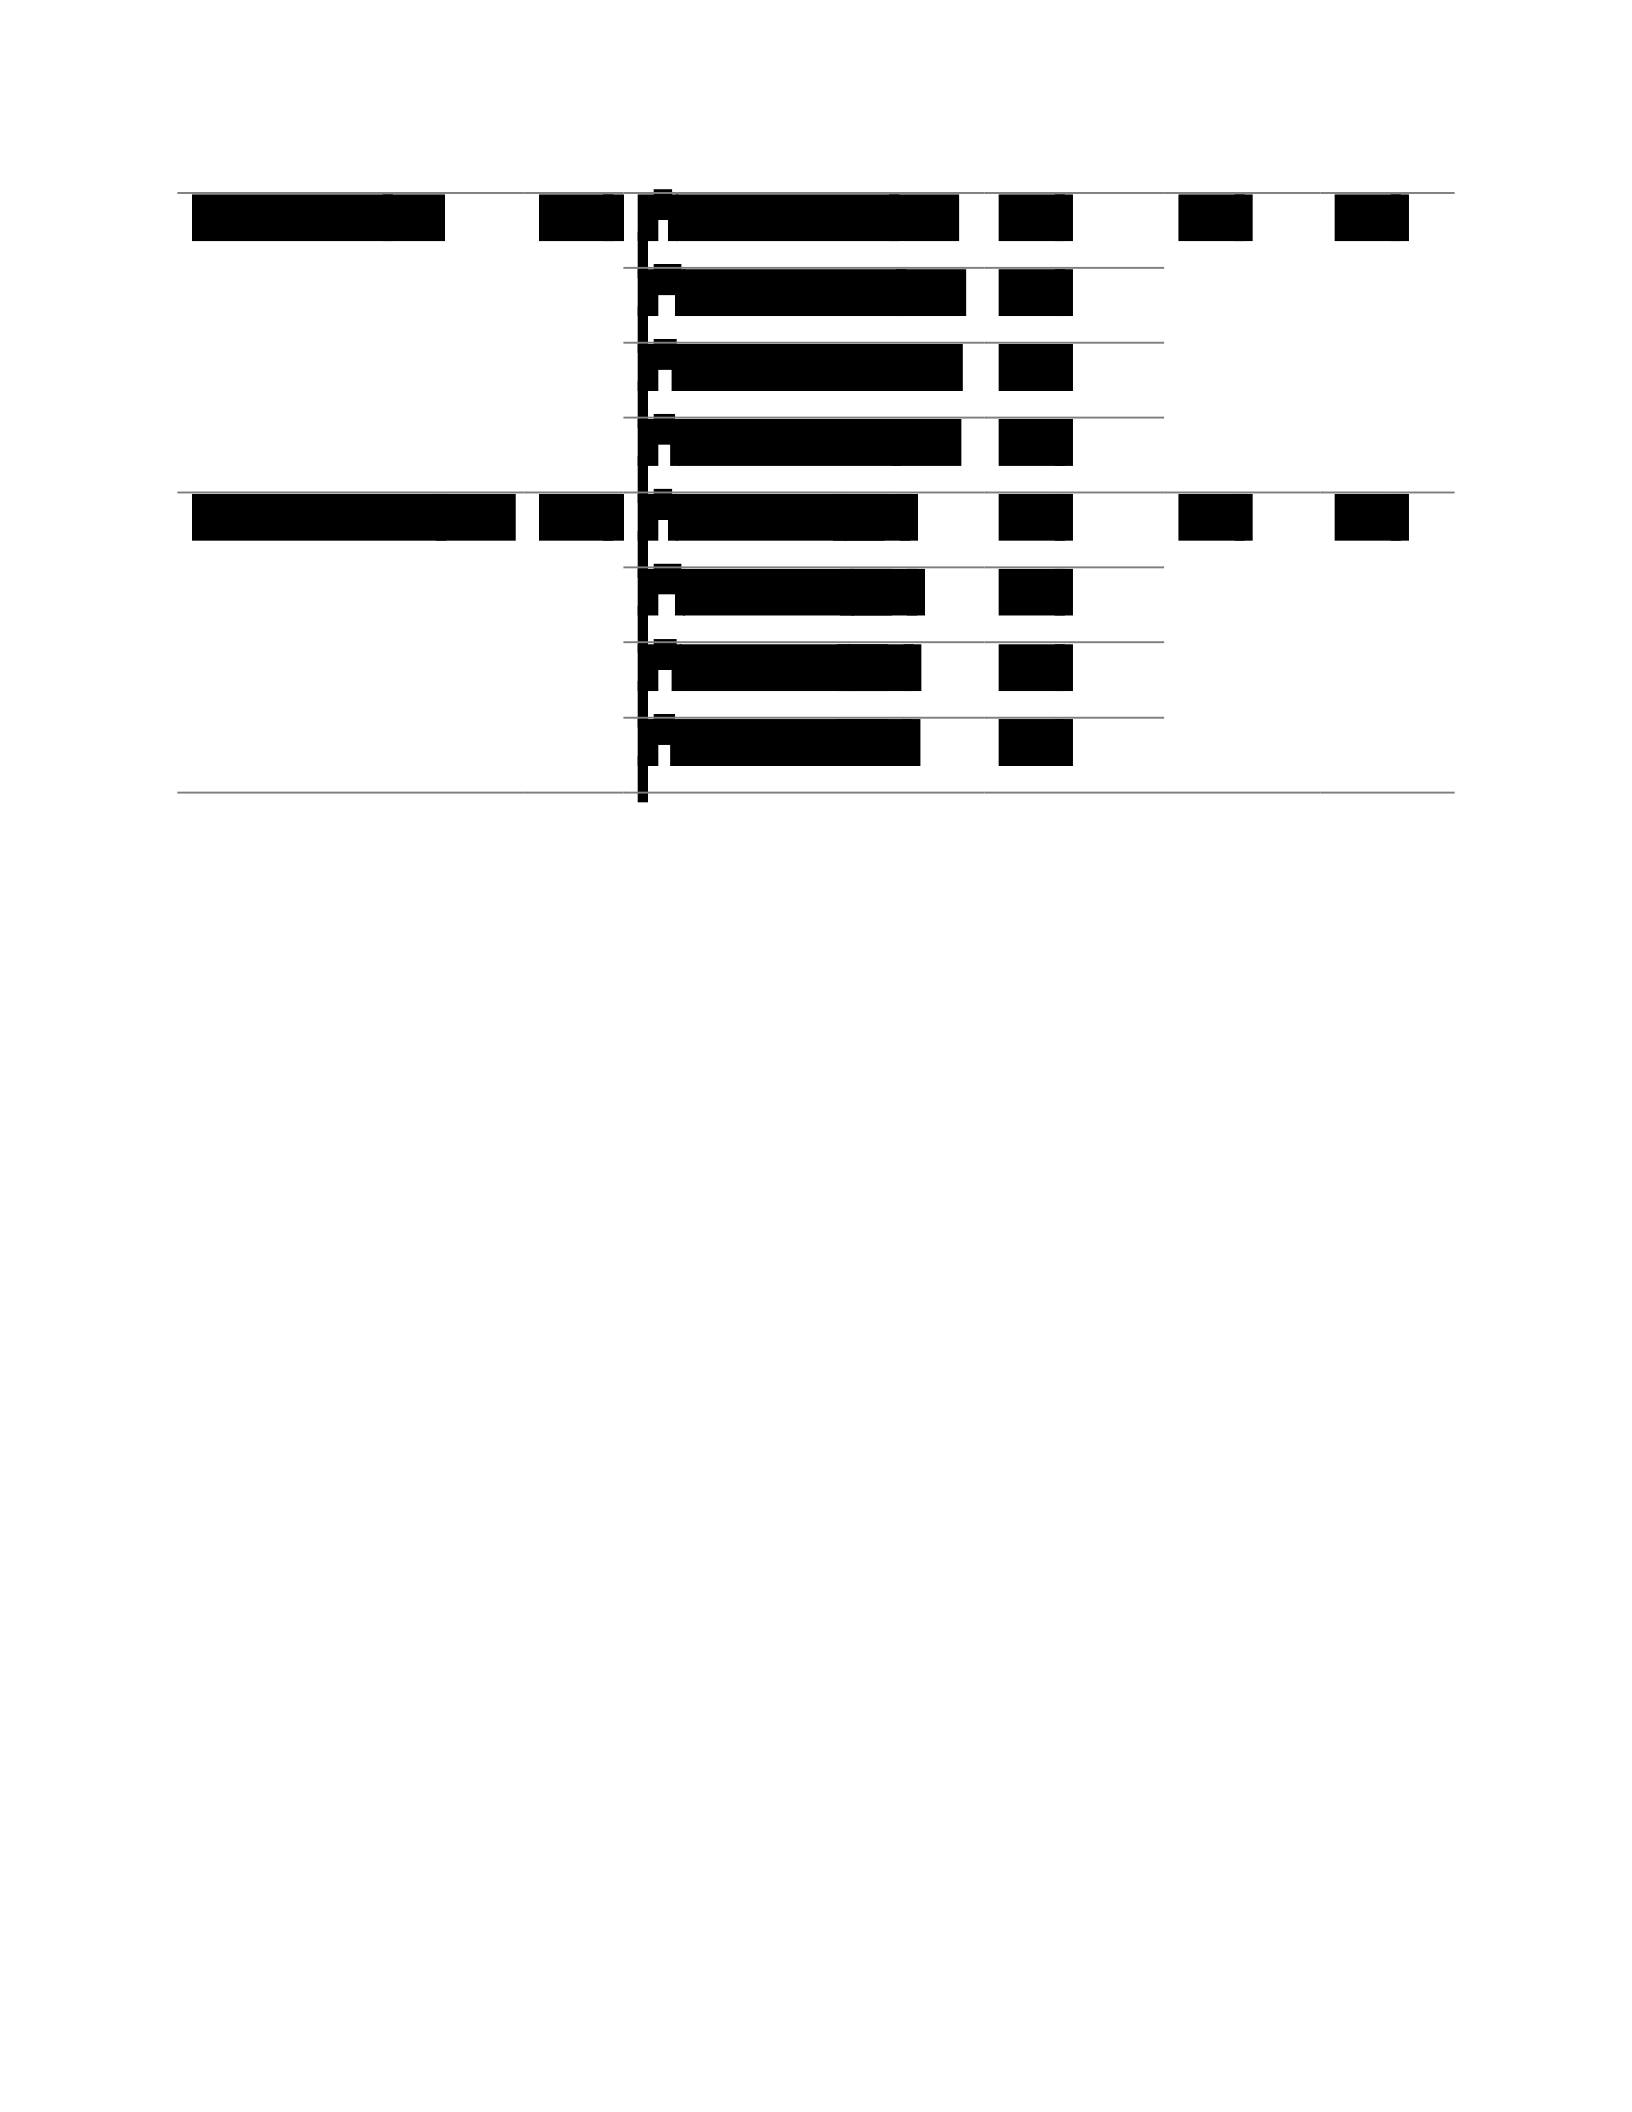
Sample Characteristics
The final sample included 6,861 participants. The majority were staff nurses (53.02%, n
= 3,638/6,861) whose primary role was direct patient care (61.01%, n = 4,186/6,861); 42.09% (n
= 2,888/6,861) reported spending 81-100% of their time seeing patients (see Table 6). The
GGNPS is intended to evaluate the use of genetics/genomics by nurses providing direct patient
care, therefore this sample is representative of the target population. The majority of participants
were female (71.05%, n = 4,875/6,861), White (62.26%, n = 4,272/6,861), and
nonHispanic/Latino (72.15%, n = 4,950/6,861) (see Table 5). A large portion (44.67%, n =
3,065/6,861) of the participants had a baccalaureate education (see Table 5). Among the
participants, 10.65% (n = 731/6,861) reported being current students (see Table 5). Participants
also reported their age (see Table 5); however, time since graduation or length of nursing career
cannot be inferred based on reported age because educational and career paths vary significantly.
The age of four participants was not reported because they incorrectly wrote 2010 or 2012 as
their birth year.
Social System
6861
1
st
Imputation: 2.33
1.50
.484
.693
2
nd
Imputation: 2.33
1.50
3
rd
Imputation: 2.31
1.49
4
th
Imputation: 2.34
1.50
Decision/Adoption
6861
1
st
Imputation:
-
1.13
2.16
.135
.939
2
nd
Imputation:
-
1.12
2.16
3
rd
Imputation:
-
1.14
2.15
4
th
Imputation:
-
1.12
2.17

Table 5
Frequency Table – Demographic Variables.
Variable
Frequency
Percent of
Participants
Percent of Participants with
Non-Responders Removed
Gender
Female
4875
71.05%
93.7%
Male
328
4.78%
6.3%
No Response
1658
24.17%
Ethnicity/Race
American Indian/Alaska Native
26
.38%
.51%
Asian
384
5.60%
7.6%
Black/African American
335
4.88%
6.63%
Native Hawaiian/Pacific Islander
34
.50%
.67%
White
4272
62.26%
84.58%
No Response
1810
26.38%
Hispanic/Latino
Yes
231
3.37%
4.46%
No
4950
72.15%
95.54%
No Response
1680
24.49%
Age
20-45 years
2354
34.31%
49.30%
46-65 years
2328
33.93%
48.76%
66+ years
92
1.34%
1.92%
No Response
2087
30.42%
Highest Nursing Degree
Associate Degree in nursing
1062
15.48%
20.36%
Baccalaureate Degree in nursing
3065
44.67%
58.77%
Diploma
324
4.72%
6.21%
Doctorate Degree in nursing
33
.48%
.63%
Master’s Degree in nursing
731
10.65%
14.01%
No Response
Are you a student?
1646
23.99%
No
4491
65.46%
86.00%

Yes
No Response
731
1639
10.65%
23.89%
14.00%
ANA Member
No
3963
57.76%
75.93%
Yes
1256
18.31%
24.06%
No Response
1642
23.93%
Table 6
Frequency Table – Clinical Experience
Variable
Frequency
Percent of
Participants
Percent of Participants with
Non-Responders Removed
Primary Area of Expertise
Case Manager
96
1.40%
1.93%
Clinical Nurse Specialist
110
1.60%
2.21%
Consultant
47
.69%
.94%
Director/Assistant Director
109
1.59%
2.19%
Educator
230
3.35%
4.62%
Head Nurse
286
4.17%
5.75%
Nurse Practitioner
185
2.70%
3.72%
Researcher
41
.60%
.82%
Staff Nurse
3638
53.02%
73.14%
Supervisor
232
3.38%
4.66%
No Response
1887
27.50%
Primary Function
Administration
464
6.76%
9.27%
Education
272
3.96%
5.44%
Patient care
4186
61.01%
83.67%
Research
72
1.05%
1.44%
Student
9
.13%
.18%
No Response
1858
27.08%
Percent Time Seeing Patients
0-20%
741
10.8%
14.82%
21-40%
256
3.73%
5.12%
41-60%
374
5.45%
7.48%
61-80%
741
10.8%
14.82%
81-100%
2888
42.1%
57.76%
No Response
1861
27.12%
Number of Years Working in
Nursing
0-3 years 1137 16.57% 21.98%
6-10 years 744 10.84% 14.38% 11-15 years 606 8.83% 11.71%
16-20 years 643 9.37% 12.43%
21-25 years 502 7.32% 9.70%
26-30 years 587 8.56% 11.35%
31-35 years 524 7.64% 10.13%
36-40 years 316 4.61% 6.11%
41-45 years 97 1.41% 1.88%
46-50 years 17 .25% .33%
No Response 1688 24.6%
Content Validity
All eight content experts completed and returned the CVI. One individual answered the
questions intended for the learners, not the content experts, and this reply was excluded. The
remaining seven responses were used to calculate the CVR using Lawshe’s formula (Lawshe,
1975):
CVR = [Ne – (N/2)]/ (N/2)
A relevance table with four categories (ranging from ‘very relevant’ to ‘not relevant’) was
used to score each item. ‘Ne’ was determined by the number of panelists who classified the item
as ‘very relevant’ or ‘relevant’ and ‘N’ is the total number of content experts. Higher CVR
values indicate a greater degree of content validity as reported by the content experts. A value of
1 indicates that all reviewers considered an item ‘very relevant’ or ‘relevant,’ lower numbers
indicate that some of the reviewers considered the items ‘somewhat relevant’ or ‘not relevant.’
The majority of the items performed well (CVR = -0.714 to 1), see Appendix E for the
CVR values of each item in the GGNPS. However, several items had lower CVR values (-0.714

to 0.428), indicating that the content experts considered these items less relevant to the
instrument. Written comments from the content experts provided additional information. These
items included:
Domain: Confidence
Item: Confidence regarding the following: “Give patients information about the
limitations of genetic testing for common diseases.”
CVR = 0.428
One content expert stated that not all RNs may be able to provide this information.
Instead RNs may be able to reinforce information provided by genetics specialists and recognize
the need for clarification.
Domain: Competency/Knowledge
Item: “Thinking about how you support clinical decisions (such as administering drugs
prescribed), how important do you think each of the following is to consider?”
CVR= 0.428
Two content experts indicated this item would need more specific information. For
example, a gene known to contribute to ovarian cancer such as BRCA1 and 2, as opposed to a
more multifactorial disease such as diabetes. The second expert added that it was unclear
whether the item was referring to medication administration or was a general question; also, that
a clinical example that required consideration for a referral may clarify the item.
Item: “The DNA sequences of two randomly selected healthy individuals of the same sex
are 90-95% identical.”
CVR= - 0.714
Regarding DNA sequence similarities among two randomly selected healthy individuals,
a content expert indicated that this item may not have clinical significance and the DNA

similarities may exceed 95% (as opposed to the 90-95% indicated by the GGNPS). However,
further analysis of this item is required because this is a ‘True/False’ item and the correct answer
is ‘False.’ At least one content expert evaluated this item with the assumption that the correct
answer was ‘True.’ As a result, additional clarification from content experts is warranted.
Item: “In describing your genetic/genomic knowledge, would you consider it to be”
CVR= 0.428
This item was considered redundant by a content expert because a previous item asks
learners to rate their understanding of the genetics of common diseases as excellent, good, or
poor.
Domain: Social Systems
Item: “Do you intend to learn more about genetics?”
CVR = 0.142
Two content experts stated that this item may overlap with the attitudes/receptivity
domain, as opposed to social systems. A third content expert stated that this item may be
misleading because she believes all participants will answer ‘yes.’
Lawshe’s method for determining content validity is widely used in a variety of fields,
including health sciences, psychology, and education. Despite its frequent use, it has some
limitations. Lawshe (1975) reported that the critical values for content validity were calculated
by Lowell Schipper. Neither Schipper nor Lawshe described the method for calculating the
values; when statisticians attempted to recreate the calculations using discrete binomials and
normal approximation to the binomial, neither exactly matched the values calculated by
Schipper. Wilson and colleagues (2012) hypothesized that variation may be due to a calculation
error, typographical error, or incorrect labeling by Lawshe. Lawshe reported critical CVR at α =

0.05, one tailed; however, the values calculated by Schipper are a closer match to a normal
approximation to the binomial at α = 0.05, two tailed (or α = 0.025, one tailed).
Lastly, Wilson and colleagues (2012) hypothesized that Schipper may have selected,
instead of calculating, that a critical CVR for n = 5, 6, 7 was 0.99, which may explain why it
does not match attempts to recalculate the values. Due to a small sample size of content experts,
he may have considered agreement among all reviewers mandatory to reach critical CVR.
However, when calculated by Wilson and colleagues (2012), using normal approximation to the
binomial, the critical CVR for n = 7 was 0.741 (p = 0.05, two tailed test). A CVR of 0.741 (n =
7) is achieved if only one content experts rates an item as ‘not relevant’ or ‘somewhat relevant.’
Therefore, both calculating the CVR using normal approximation to the binomial and
consideration that all, except one, content experts consider the item ‘relevant’ or ‘very relevant’
is the basis for considering items achieving a score of 0.741 or greater as relevant to the GGNPS.
A comprehensive CVI was computed as the mean of the content validity ratios across all
items. The range for agreement varied among content experts, -0.714 to 1 (see Appendix E). The
overall CVI was 0.805, exceeding 0.741, which Wilson and colleagues (2012) identified as the
required threshold when seven content experts evaluate an instrument. This information was also
used in the ancillary analysis in combination with results from the exploratory factor analysis
(EFA) to evaluate items considered for removal from the instrument.
Face Validity
Face validity was conducted with seven reviewers. All reviewers were nurses with a
variety of clinical and educational backgrounds. Educational backgrounds varied from associate
to doctoral degrees (see Table 7). Number of years in clinical practice varied from 2 to 31 years.
None of the reviewers had specific education or expertise in genetics/genomics. Reviewers
without genetics/genomics expertise were selected to provide the perspective of the majority of

nurses in the workforce. The GGNPS was created to evaluate the clinical applications of
genetics/genomics; therefore, reviewers who spend the majority of their time seeing patients
were selected. Face validity was conducted to evaluate the ease of understanding and applying
the instrument to nursing practice.
Most of the participants reported that the GGNPS was somewhat clear/easy to understand
(n = 5/7); others reported that it was very clear/easy to understand (n = 2/7) (see Table 7). The
majority of participants (n = 5/7) reported that the items were pertinent to their clinical practice
(see Table 7). Feedback from the reviewers indicated the GGNPS has face validity.
(3ng/poy)
Aseo/reo]3
area
osInN
ON
Sox
yeyMowlos
S
,JO\Sey|
quoned
%OL
peoyH Or L
Aseo/1ea[o
aed
SOX Sox
yeyMowos
S
,JO]SeJ|
quoned
%OOI
OSINN
JJRIS
IZ 9
Jouon
Aseo/1eo[o
-oelg
Sox Sox
AINA,
S
Josey
uoneonpy
“Or
osINN
I¢
¢
Asea/teayo
aed
Sox Sox
yeYMOUIOS
91210}90q
quoned
%OOT
OSINN
JJeIS
0
v
Aseo/teayo
(aa)
area
ON
ON
yeYMOUIOS
oyeomneypeooeg
quoned
%09
OSINN
JJeIS
Z
€
Aseo/teayo
(NOD
2Re9
ON
sox
yeYMOUIOS
oyeomneypeooeg
quoned
%OOT
OSINN
JJeIS
v Z
Aseo/1eo]o
ored
ON
ON
AIO.
a1e1D0SsV
quoned
%001
9SINN
FPS
0€
I
gsonoeid
sulsinu
[eorurys
ano
{puejsiopun
0} ul
ursormouss
«goonoevid
jeorurja
sea
pu
reajo
sonjoeid
syuoryed
Roly
SuLyIOM
/sonouss
NoK
0}
JuOUTVIOd
quouNsUI
seISop
Sursinu
jovoie
Suloosoum
yeuonouny
sieaX
Jo
asn
noAoq
suonsonb
oj
ory
ou}
Ss]
ysoysty
Areulig
uonsjodolg
Aeulig
JOquUNN
JOMOIADY
‘sy[nsoy
Ape
A
90ey
LAqeL
70

68
Construct Validity
Hypothesis 1.
Confirmatory Factor Analysis results will show that:
a. GGNPS items Part 2, Questions 2.1, 2.2, 2.4; Part 4, Questions 1, 2, 3; Part 5,
Questions 1, 2; Part 6, Questions 1, 2 comprise the underlying latent variable of
COMPETENCY/ KNOWLEDGE.
b. GGNPS items Part 1, Questions, 1, 2, 3; Part 2, Questions 2, 3 comprise the
underlying latent variable of ATTITUDES/RECEPTIVITY.
c. GGNPS items Part 3, Questions 2, 3, 4 comprise the underlying latent variable of
DECISION/ADOPTION.
d. GGNPS item Part 2, Question 1 comprises the underlying latent variable of
CONFIDENCE.
e. GGNPS item Part 7, Questions 1.3, 1.4, 1.5, 1.6, and 1.7 comprise the underlying
latent variable of SOCIAL SYSTEM.
A CFA was conducted to evaluate whether the respective GGNPS items comprised the
underlying variables. The CFA was conducted with the original data set (with missingness
handled through listwise deletion in MPLUS) and with the four data sets imputed through the
Mice package in R. Conducting the analysis with five models, the original data and four
imputations, allowed comparison between versions of imputed data. Multiple imputations were
evaluated for consistency among the results. MPLUS, version 7.3, was used to compute both the
CFAs and structural equation models, conducted full information maximum likelihood
estimations of the missing data; this is the default setting for MPLUS to handle missing-at-random
or not-missing-at-random missing ordinal and nominal data (Muthén and Muthén, 2012) and is
the optimal method for these data. After, e.g., 34 hours and 38 minutes, and 460 iterations,

69
MPLUS reported that the models did not converge on a stable set of parameter estimates, as a
result no stable factor loadings can be reported.
Hypothesis 2.
Structural equation model (SEM) fit to data. Testing the SEM using item-level entities
required more computing power than could be achieved; therefore, the analyses were conducted
in two steps. The first step was the creation and evaluation of factor scores (by combining the
items associated with each variable); this was followed by a series of models to test the relation
between factors. SEMs are reported for the original data (see Figure 7) and the imputed data sets
(see Appendices F.1-F.4).
A SEM evaluated the proposed relations (see Figure 7). The proposed model did not fit
the collected data using χ-square as an initial fit test (see Table 8). The large χ-square (451.979, p
< .001) indicates a poor fit of the model to the data. However, because χ-square is often
significant in large sample sizes (Hooper, Coughlan, & Mullen, 2008), other measures of fit were
analyzed. Root mean square error of approximation (RMSEA) is an evaluation of fit that
considers sample size. An RMSEA ≤ 0.05 is typically regarded as indicating a very good fit and
≤ 0.08 is considered to indicate an acceptable fit (Browne et al., 1993). In the original data set
and the four variations of imputed data, none of the models indicated a good fit (see Table 8).
The Comparative Fit Index (CFI) compares a posed model with a null model and CFI indices
range between 0 and 1. Values ≥ 0.9 indicate a good model fit (Davis & Murrell, 1993). In the
original data set and the four variations of imputed data, none were greater than 0.9 (see Table 8).
Bayesian Information Criterion (BIC) is also a comparative fit measure between models that
corrects for the number of parameters in a model as well as the sample size (Raftery, 1993). A
low BIC value indicates a better model fit. Among the original data set and the four variations of
imputed data, the BICs ranged from 79,506.863-139,625.503 (see Table 8). Multiple fit

70
evaluations including χ-square, RMSEAs, CFIs, and BICs all indicated that the hypothesized
model did not fit the data. Furthermore, the poor fit was consistent across the original data set
and all four imputations.
Table 8
Model Fit Using the Original Data Set and Multiple Imputations.
Original Data Set
Imputed 1
Imputed 2
Imputed 3
Imputed 4
Chi-square
451.979
df= 3 p
<.001
603.970
df= 3 p
< .001
657.126
df= 3 p
< .001
617.126
df= 3 p
< .001
593.837
df= 3 p
< .001
RMSEA
.170
.160
.167
.162
.159
CFI
.839
.875
.871
.872
.877
BIC 79,506.863 139,302.730 139,205.026 139,625.503 139,297.560
R2 illustrates how much of the variance was explained by the model (see Table 9). This
includes the original data set and multiple imputations. Despite the fact that a statistically
significant amount of variance was explained by the model, the normalized residuals for the
covariances and correlations indicate a significant amount of residual variance was not addressed
(see Table 10).
Table 9
R2 square Values for Original Data and Multiple Imputations.
Original Data
Imputation 1
Imputation 2
Imputation 3
Imputation 4

71
Attitude/
Receptivity
R2 = .031 p
< .001
R2 = .029
p < .001
R2 = .040
p < .001
R2 = .030 p
< .001
R2 = .031
p < .001
Confidence
R2 = .202 p
< .001
R2 = .152
p < .001
R2 = .153
p < .001
R2 = .148 p
< .001
R2 = .146 p
< .001
Knowledge/
Competency
R2 = .166 p
< .001
R2 = .133
p < .001
R2 = .149
p < .001
R2 = .138 p
< .001
R2 = .135 p
< .001
Decision/
Adoption
R2 = .134 p
< .001
R2 = .184
p < .001
R2 = .180
p < .001
R2 = .179 p
< .001
R2 = .190 p
< .001
Table 10
Normalized Residuals for the Original Data and Multiple Imputations.
Original
Data
Imputation 1
Imputation 2
Imputation 3
Imputation 4
Decision/Adoption
and Confidence
16.50
16.76
17.01
16.80
16.56
Social systems and
Confidence
5.52
6.60
7.25
6.33
7.18
Knowledge/
Competency and
Decision/Adoption
12.19
15.85
16.45
16.15
15.4
Individual Variable Fit
Figure
SEM Using the Original Data Set.

72
p* < 0.001; p** = 0.013
Hypothesis 2a. COMPETENCY/KNOWLEDGE of genetics/genomics has a
statistically significant direct effect on one’s ATTITUDES/RECEPTIVITY and
CONFIDENCE. COMPETENCY/KNOWLEDGE has a statistically significant indirect
effect on one’s DECISION/ADOPTION of genetics/genomics.
In both the original and imputed data, there was a statistically significant direct effect of
competency/ knowledge on attitudes/receptivity (see Figure 7 and Appendices F.1-F.4).
However, considering the large sample size, the effect size was small, indicating a weak relation
between competency/ knowledge on attitudes/receptivity (.104). The original and imputed data
demonstrated a statistically significant direct effect of competency/ knowledge on confidence
(.399) (see Figure 7 and Appendices F.1-F.4). The indirect relation (-.023) between competency/
knowledge and decision/adoption (see Table 11) was negative and weak.
Social Systems
Competency
/Knowledge
Attitudes/Receptivity
Decision/Adoption
Confidence
0
.391*
0.150*
0.717*
0.399
*
-
0.039**
0.104*
-
0.225*

73
Hypothesis 2b. ATTITUDES/RECEPTIVITY has a statistically significant direct
effect on one’s DECISION/ADOPTION of genetics/genomics.
The relation between attitudes/receptivity on decision/adoption was -.225 (see Figure 7),
the relation for imputed data is described in Appendices F.1-F.4).
Hypothesis 2c. SOCIAL SYSTEMS has a statistically significant direct effect on
COMPETENCY/KNOWLEDGE, ATTITUDES/RECEPTIVITY, and
DECISION/ADOPTION and a statistically significantly indirect effect on one’s
ATTITUDES/RECEPTIVITY and DECISION/ADOPTION of genetics/genomics.
The relation between social systems and competency/ knowledge (.717) was statistically
significant and the strong (see Figure 7 and Appendices F.1-F.4). By contrast, the relation
between social systems and attitudes/receptivity (.150) was weak, although statistically
significant (see Figure 7 and Appendices F.1- F.4). The indirect relation between social systems
and decision/adoption (.034) was a negative and weak relation (see Table 11).
Hypothesis 2d. CONFIDENCE has a statistically significant direct effect on
ATTITUDES/RECEPTIVITY, and a statistically significant indirect effect on
DECISION/ADOPTION of genetics/genomics.
The direct relation between confidence and attitudes/receptivity (.039) was the weakest
relation in the SEM and was not statistically significant in imputed data set 1 (see Figure 7 and
Appendices F.1-F.4). The indirect relation between confidence and decision/adoption (.0008) the
weakest indirect relation in the SEM (see Table 11).
Table 11
Indirect Path Model Relations.
Original
Data
Imputation
1
Imputation
2
Imputation 3
Imputation
4
Competency/
Knowledge &
Decision/Adoption
-.023
-.020
-.030
-.023
-.026
74
Social Systems
&Attitudes/Receptivity
.075
.039
.061
.046
.050
Social Systems &
Decision/Adoption
-.034
-.084
-.091
-.083
-.082
Confidence &
Decision/Adoption
.0088
.0084
.011
.015
.012
Ancillary Analysis
Expert review supported the content validity and evaluation by a sample of RNs
supported face validity of the GGNPS. However, construct validity could not be established.
The CFA did not converge on a stable set of parameter estimates and reliable factor loadings
could therefore not be estimated. Similarly, the overall SEM model did not fit the data well and
many proposed relations, though statistically significant, were weak given the large sample size
and thus large power.
Due to these conflicting results between content and construct validity, a data driven
exploratory factor analysis (EFA) was conducted to compare factor loadings to the five proposed
variables in the GGNPS. Thus, a five-factor model was requested. Oblique rotation was used to
allow for factors to be related to each other (Osborne, 2015).
Criteria used for evaluation were factor loadings ≥.30 (Costello & Osborne, 2005) or
higher and presence of Thurstone’s (1947) simple structure. Thurstone’s simple structure
requires that 1) each row in a rotated factor matrix contains at least one loading near zero, 2)
among the columns there should be factors with zero loadings and other factors with higher
loadings, 3) variables should load on one factor (Plichta, Kelvin, & Munro, 2013; Thurstone,
1947).
Results
The EFA results for originally designated items (e.g., confidence, attitudes/receptivity
etc.) indicate that a). confidence items consistently load onto Factor 1, b). attitudes/receptivity

75
items and items from competency/ knowledge that are related to nurses’ attitudes regarding
genetics/genomics load onto Factor 2, c). decision/adoption items and items from
attitudes/receptivity that are related to perceived disadvantages of adopting genetics/genomics
into nursing practice load onto Factor 3, d). many competency/ knowledge items load onto Factor
4, specifically items related to collection of family history information, e). competency/
knowledge items also load onto Factor 5, specifically items related to clinical decision making
(see Table 12). Notably, social system items did not consistently load onto any single factor,
some items loaded on two other factors, while other items did not load above .30.
Table 12
Factor Loading Overview.
GGNPS Variable
Factor 1
Confidence
Factor 2
Attitudes/receptivity
Factor 3
Decision/adoption
Factor 4
Competency/knowledge 1
Factor 5 Competency/knowledge 2
Factor 1: Of the 14 GGNPS-designated confidence items (Calzone et al., 2014), all but
one item met both the loading criteria (≥ .30) and demonstrated Thurstone’s simple structure (see
Table 13). Item P2_Q1_05, asking nurses to rate their confidence in providing emotional
followup support after family history assessment, loaded most strongly on Factor 1 (.670) it also
loaded above .30 (.308) on Factor 2 (attitudes/receptivity).
Table 13
EFA Results for GGNPS-Designated Confidence Items.

76
Item
1
2
3
4
5
P2_Q1_01
Decide what family history information is
needed to tell something about a patient’s genetic
susceptibility to common diseases.”
.751*
.115
.232
.281
-.190
P2_Q1_02
Use family history information to support
treatment decisions for patients who have
common diseases.”
.742*
.138
.232
.288
-.180
P2_Q1_03
Counsel patients about inherited risk for
common diseases.”
.758*
.105
.183
.194
-.127
P2_Q1_04
Assure that patient’s family history information
relating to common diseases remains
confidential.”
.383*
.283
-.009
.015
-.133
P2_Q1_05
Provide emotional follow-up support after family
history assessment.”
.670*
.308
-.116
-.035
-.124
P2_Q1_06
Discuss how family history affects recommended
screening intervals.”
.768*
.106
.096
.132
-.080
P2_Q1_07
Decide which patients would benefit from a
referral for genetic counseling and possible
testing for susceptibility to common diseases.”
.817*
.019
.026
.115
.002
P2_Q1_08
Access reliable and current information about
genetics and common diseases.”
.755*
.018
-.036
.057
.023
P2_Q1_09
Provide information about the availability of
genetic testing for common diseases.”
.882*
-.093
-.053
-.050
.145
P2_Q1_10
Give patients information about the risks of
genetic testing for common diseases.”
.925*
-.105
-.017
-.073
.173
P2_Q1_11
Give patients information about the benefits of
genetic testing for common diseases.”
.925*
-.074
-.008
-.074
.162

77
P2_Q1_12
Give patients information about the limitations
of genetic testing for common diseases.”
.931*
-.109
-.013
-.081
.180
P2_Q1_13
Facilitate referrals for genetic services for common
diseases.”
.817*
-.052
-.093
-.006
.123
P2_Q1_14
Provide emotional follow-up support after genetic
testing.”
.716*
.220
-.149
-.068
-.044
* Highest loading. Bolded items loaded ³ .30.
Factor 2: Of the 17 GGNPS-designated attitude/receptivity items (Calzone et al., 2014),
six loaded onto Factor 2 (see Table 14). These were items related to the potential advantages of
genetics/genomics. Eight items of the 17 GGNPS-designated attitude/receptivity items loaded on
Factor 3. These items related to potential disadvantages of genetics/genomics and are discussed
below. Concerning the remaining three items, item P1_Q3_06 (would increase insurance
discrimination) was excluded from the EFA because the item did not demonstrate any variation
and thus provided no information about associations. All participants, except those who left the
item blank, responded “yes” indicating this was a perceived disadvantage of genetics/genomics.
The remaining two items did not load above .30 on any factor and did not demonstrate
Thurstone’s simple structure. These items were, P1_Q1 (importance of nurses to become
educated about genetics of common diseases) and P1_Q3_04 (if a potential disadvantage of
integrating genetics is that it would not improve patient care). Item P2_Q3_03 (family history
taking should be a key component of nursing care) loaded ³ .30 on Factor 4
(competency/knowledge 1) as well as .375 on Factor 2 (attitudes/receptivity). The other items
demonstrated Thurstone’s simple structure. Eight, out of 25, GGNPS-designated
competency/knowledge items loaded onto Factor 2 (see Table 16). However, these were items
can be considered related to nurses’ attitudes regarding genetics/genomics. For example, asking
nurses if they think genetic risk is associated with a variety of clinical conditions.

78
Table 14
EFA Results for GGNPS-Designated Attitudes/Receptivity Items.
Item
1
2
3
4
5
P1_Q1
How important do you think it is for the nurse to
become more educated about the genetics of
common diseases?”
.155
.282*
-.058
.198
.151
P1_Q2_01
Potential advantages of integrating genetics: Better
decisions about recommendations for
preventative services.”
.042
.377*
.206
.153
.106
P1_Q2_02
Potential advantages of integrating genetics: Better
treatment decisions.”
.053
.314*
.190
.070
.122
P1_Q2_03
Potential advantages of integrating genetics:
Improved services to the patients.”
-.020
.306*
.094
.077
.120
P1_Q2_04
Potential advantages of integrating genetics: Better
adherence to clinical recommendations among
patients.”
.013
.343*
.218
.114
.133
P1_Q2_05
Potential advantages of integrating genetics:
Genetic risk triaging could make better use of
visit time.”
.064
.325*
.186
.118
.151
P1_Q3_01
Potential disadvantages of integrating genetics:
Would take too much time.”
-.045
-.124
.369*
-.022
.063
P1_Q3_02
Potential disadvantages of integrating genetics:
Not reimbursable/Too costly.”
.040
.028
.397*
.070
.045
P1_Q3_03
Potential disadvantages of integrating genetics:
Need to ‘re-tool’ professionally.”
-.027
.013
.321*
.018
.057
P1_Q3_04
Potential disadvantages of integrating genetics:
Would not improve patient care.”
-.004
-.292*
.157
-.118
-.120
P1_Q3_05
Potential disadvantages of integrating genetics:
Increase patient anxiety about risk.”
-.046
.013
.330*
.072
-.03

79
P1_Q3_07
Potential disadvantages of integrating genetics:
Medical-legal problems for nurses related to
testing.”
-.014
-.005
.430*
.038
.057
P1_Q3_08
Potential disadvantages of integrating genetics:
Greater burden of responsibilities on nurses.”
-.067
-.051
.448*
-.076
.042
P1_Q3_09
Potential disadvantages of integrating genetics:
Need to educate nurses in genetics.”
-.142
.059
.370*
.032
.031
P1_Q3_10
No disadvantages.”
.110
.121
-.657*
-.071
.009
P2_Q3_03
Family history taking should be a key component
of nursing care.”
.072
.375*
-.144
.304
.028
*Item P1_Q3_06 “Would increase insurance discrimination” is not included because there was
no variation in the responders’ reply.
Factor 3: Analysis of the EFA results indicates Factor 3 relates to decision/adoption. Of
the 12 GGNPS-designated decision/adoption items, eight loaded onto Factor 3 (see Table 15).
Those items also demonstrated Thurstone’s simple structure. Of the remaining four items, one
item, P3_Q3 (in the past 3 months, has any patient initiated a discussion with you about
genetics), did not load above .30 on any factor (see Table 15) and three items designated as
decision/adoption in the GGNPS loaded onto Factor 4 (competency/knowledge 1) and are
discussed below. As previously noted in the Factor 2 section, eight of the 17 GGNPS-designated
attitude/receptivity items, loaded onto Factor 3 (decision/adoption), see Table 14. These items
related to potential disadvantages, and therefore also perhaps related to the decision to adopt
genetics and genomics.
Table 15

80
EFA Results for GGNPS-Designated Decision/Adoption Items.
Item
1
2
3
4
5
P2_Q2_01
Limitations of discussing genetics with
individuals “My difficulty finding information on
genetics and common diseases.”
-.070
.065
.448*
-.021
.076
P2_Q2_02
Limitations of discussing genetics with
individuals “Lack of time to get a patient’s
complete family history.”
.058
-.038
.523*
-.085
.081
P2_Q2_03
Limitations of discussing genetics with
individuals “No reimbursement for counseling or
testing.”
.143
-.025
.564*
.077
.097
P2_Q2_04
Limitations of discussing genetics with
individuals “No place to send patients for
counseling or testing.”
.072
.069
.582*
-.001
.052
P2_Q2_05
Limitations of discussing genetics with
individuals “Increased nursing liability.”
.073
-.091
.606*
-.075
.114
P2_Q2_06
Limitations of discussing genetics with
individuals “Not in my scope of practice.”
-.140
-.006
.363*
-.153
-.009
P2_Q2_07
Limitations of discussing genetics with
individuals “My limited expertise in genetics.”
-.297
.291
.435*
-.057
-.006
P2_Q2_08
Limitations of discussing genetics with
individuals “Lack of use of genetics in my
clinical area.”
-.146
.184
.446*
-.121
-.004
P3_Q2
In the past 3 months, how often have you collected a
complete family history …”
.191
-.057
-.040
.401*
.099
P3_Q3
In the past 3 months, has any patient initiated a
discussion with you about genetics?”
.182
-.006
-.182
.297*
.023
P3_Q4_01
In the past 3 months, how often have you used
family history information when facilitating
clinical decisions or recommendations for your
patients?”
.197
.053
-.065
.402*
.044
81
P3_Q4_02
In the past 3 months, how often have you facilitated
referrals to genetic services?”
.264
-.139
-.246
.318*
.099
Factor 4: Analysis of the EFA results indicates Factor 4 relates to
competency/knowledge. However, of the 25 GGNPS-designated competency/knowledge items
(Calzone et al., 2014), only seven loaded on Factor 4 (see Table 16). These were items related to
collection of family history information. As previously noted, 8 GGNPS competency/knowledge
items loaded on Factor 2 (attitudes/receptivity) and as noted below six competency/knowledge
items loaded on Factor 5(competency/knowledge 2). The remaining four GGNPS-designated
competency/knowledge items did not have a loading above .30 or did not have simple structure.
These included items P2_Q3_01, P5_Q1, P5_Q2, and P6_Q1 (see Table 16). These items were
related to family history collection for new patients, knowledge of the Essential Competencies
and Curricula Guidelines for Nurses in Genetics and Genomics, and information regarding the
structure and function of genetic material.
In addition to competency/knowledge designated items, one of the five
GGNPSdesignated social system items loaded on Factor 4; item P7_Q1_01 (“do you intend to
learn more about genetics”). Finally, Factor 4 also includes three GGNPS-designated
decision/adoption items, P3_Q2, P3_Q4_01, P3_Q4_02 (see Table 16). These three items
explore nursing actions in the past three months related to collection and use of family history
information, as well as facilitating referrals to genetic services.
Factor 5: The EFA results indicate that Factor 5 also relates to competency/knowledge.
Of the 25 GGNPS-designated competency/knowledge items (Calzone et al., 2014), six loaded on
Factor 5. These were items related to clinical decision making.
Table 16

82
EFA Results for GGNPS-Designated Competency/Knowledge Items.
Item
1
2
3
4
5
P2_Q3_01
A family history that includes only 1st degree
relatives such as parents, siblings, and children
should be taken for every new patient.”
-.076
-.173*
-.027
-.056
.002
P2_Q3_02
A family history that includes 2nd and 3rd degree
relatives such as grandparents, aunts, uncles, and
cousins should be taken for every new patient.”
.078
0.307*
-.111
.252
.021
P2_Q3_04
There is a role for nurses in counseling patients
about genetic risks.”
.144
.339*
-.166
.232
.045
P4_Q1_01
Do you think genetic risk has clinical relevance
for: Breast cancer.”
-.020
.923*
-.002
.011
.016
P4_Q1_02
Do you think genetic risk has clinical relevance
for: Colon cancer.”
.001
.880*
.002
.001
.013
P4_Q1_03
Do you think genetic risk has clinical relevance
for: Coronary heart disease.”
-.033
.826*
-.013
.007
.028
P4_Q1_04
Do you think genetic risk has clinical relevance
for: Diabetes.”
-.018
.786*
-.007
-.011
.037
P4_Q1_05
Do you think genetic risk has clinical relevance
for: Lung cancer.”
.017
.646*
-.011
-.076
.139
P4_Q1_06
Do you think genetic risk has clinical relevance
for: Ovarian cancer.”
.016
.778*
-.025
-.032
.066
P4_Q2_01
When patients indicate a disorder in the
family, which information do you collect in
your standard family history assessment:
“Age at diagnosis of condition”
.022
-.129
-.023
.836*
.007

83
P4_Q2_02
When patients indicate a disorder in the
family…: “Relationship to the patient.”
-.159
.044
.029
1.019*
-.204
P4_Q2_03
When patients indicate a disorder in the
family…: “Race or ethnic background.”
.047
-.085
.004
.660*
.101
P4_Q2_04
When patients indicate a disorder in the
family…: “Age at death from condition.”
-.020
-.147
.006
.900*
-.029
P4_Q2_05
When patients indicate a disorder in the
family…: “Both sides of the family
(maternal/paternal).”
-.111
.005
-.013
.951*
-.150
P4_Q4_01
Which of the following is important to
consider in clinical decision-making:
“Gender.”
-.019
.063
.045
0
.885*
P4_Q4_02
Which of the following is important to
consider in clinical decision-making:
“Race/Ethnicity.”
-.008
.060
.050
.008
.912*
P4_Q4_03
Which of the following is important to
consider in clinical decision-making:
“Genes.”
.012
.087
-.020
.086
.851*
P4_Q4_04
Which of the following is important to
consider in clinical decision-making: “Family
history.”
-.004
.127
-.003
.108
.820*
P4_Q4_05
Which of the following is important to
consider in clinical decision-making: “Age.”
-.028
.175
.008
.078
.496*
P4_Q4_06
Which of the following is important to
consider in clinical decision-making:
.059
-.022
.030
.130
.328*
“Insurance Status.”
P5_Q1
The DNA sequences of two randomly selected
healthy individuals of the same sex are 90-95%
identical.”
.118*
-.101
.041
.111
.033
P5_Q2
Most common diseases such as diabetes and
heart disease are caused by a single gene
variant.”
.102
-.092
.014
.132*
.016

84
P6_Q1
The Essential Competencies and Curricula
Guidelines for Nurses in Genetics and
Genomics are endorsed as being a standard
part of nursing practice. Have you heard or
read about these Competencies?”
.199
-.150
-.108
.281*
.154
P6_Q2_01
Please rate your understanding of the genetics
of common diseases.”
.445
-.354
.010
.496*
.119*
P6_Q2_02
In describing your genetic/genomic knowledge,
would you consider it to be.”
.445
-.375
-.003
.491*
.139
The GGNPS-designated social system items did not load predominantly onto one factor
(see Table 17). Item P7_Q1_01 loaded onto Factor 4. Two items, P7_Q1_02 (would you be able
to attend a course during work hours) and P7_Q1_03 (would you attend a course on your own
time) did not contain a loading above .30 and did not contain simple structure. Items P7_Q1_04
(do you think your senior staff members see genetics as an important part of your role) and
P7_Q1_05 (do you think your senior staff members see genetics as an important part of their
role) loaded ³ .30 on both Factors 3 (decision/adoption) and 4 (competency/knowledge).
Furthermore, both items P7_Q1_04 and P7_Q1_05 included negative loadings (see Table 17). A
negative factor loading indicates an inverse relation between the item and the factor. Social
systems may be pervasive throughout the other variables, as opposed to being an independent
variable.
Table 17
EFA Results for GGNPS-Designated Social System Items.
Item
1
2
3
4
5
85
P7_Q1_01
Do you intend to learn more about genetics?”
.059
.198
-.173
.308*
.137
P7_Q1_02
Would you be able to attend a course during work
hours?”
.027
.108
-.130
.116*
.114
P7_Q1_03
Would you attend a course on your own time?”
.027
.198
-.142
.215*
.091
P7_Q1_04
Do you think your senior staff members see genetics
as an important part of your role?”
.001
.082
-.633*
.387
.160
P7_Q1_05
Do you think your senior staff members see genetics
as an important part of their role?”
-.024
.092
-.635*
.370
.141
Factor loadings and simple structure results were also evaluated with CVRs, analyzing
EFA data with content validity expert input (see Table 18). Many items with loadings below .30
had high CVRs. In addition, these items contained important content, such as how to collect
family history information. Since they did not load above .30 in the EFA, they would be
recommended for deletion based on Thurstone’s simple structure; however, in consideration with
evaluation by the content experts they are recommended for revision. By contrast, item P5_Q1
had a low factor loading, lack of simple structure, and low CVR, it is recommended for deletion
or revision (see Table 18).
Table 18
Items with Low Factor Loadings and Associated CVRs.
Item
Highest
Loading
Simple
Structure
CVR

86
P1_Q1
“How important is it for the nurse to become more
educated about the genetics of common diseases?”
.282
Absent
1
P1_Q3_04
“Potential disadvantages: would not improve patient
care.”
.292
Absent
N/A
P2_Q3_01
“A family history that includes only 1st degree relatives
such as… should be taken for every new patient.”
(shortened)
-.173
Absent
.714
P5_Q1
“The DNA sequences of two randomly selected healthy
individuals of the same sex are 90-95% identical.”
.118
Absent
-.714
P5_Q2
“Most common diseases such diabetes and heart
disease are caused by a single gene variant”
.132
Absent
1
P6_Q1
“Have you heard of the Essential Competencies… in
Genetics and Genomics?” (shortened)
.281
Absent
0.714
P7_Q1_02
“Would you be able to attend a course during work
hours?”
.116
Absent
1
P7_Q1_03
“Would you be able to attend a course on your own
time?”
.215
Absent
.714
Analyses support that the GGNPS does have content and face validity. However,
statistical analyses also indicate that the constructs in the GGNPS may be more interrelated than
originally hypothesized. A number of items from competency/knowledge loaded on
attitudes/receptivity. In addition, attitudes/receptivity items related to perceived disadvantages
loaded onto decision/adoption. Some social systems items did not load well on a single factor,
while others loaded on multiple factors simultaneously. This may indicate that social systems
pervade throughout the other variables, as opposed to being an independent variable. Results of
the EFA also provide insight into why the CFA was unable to load on a stable set of parameters.
Many items loaded on factors different than those originally designated in the GGNPS. Further

87
analysis of how items in the GGNPS are related to the underlying variables can support future
analysis of construct validity.

88
Chapter V
Discussion
This study proposed to test the face, content, and construct validity of the GGNPS
developed by Calzone and colleagues (2012, 2016, 2014). The GGNPS is based on Rogers’
(2003) DOI theoretical framework and model, as well as Calzone and colleagues’ (2012) work,
which added confidence as a variable in the adoption of genetics/genomics into nursing practice.
Construct validity was explored in two ways, CFA and SEM analyses. The SEM was based on
the current study’s hypothesized model (see Figure 8), which stemmed from the works of Rogers
(2003) and Calzone and colleagues (2012; 2007).
Figure 7
Hypothesized Model.
Results indicate that the GGNPS has both content and face validity. However, construct
validity was not established. The CFA did not converge on a stable set of parameter estimates
and thus factor loadings could not be estimated. In addition, the SEM showed that this study’s
hypothesized model did not fit the data. However, the SEM did provide insight into the relations
between/amongst the model’s variables, though many of these relations were weak considering
the large sample size.
Social
Systems
Competency
/Knowledge
Attitudes/Receptivity
Decision/Adoption
Confidence
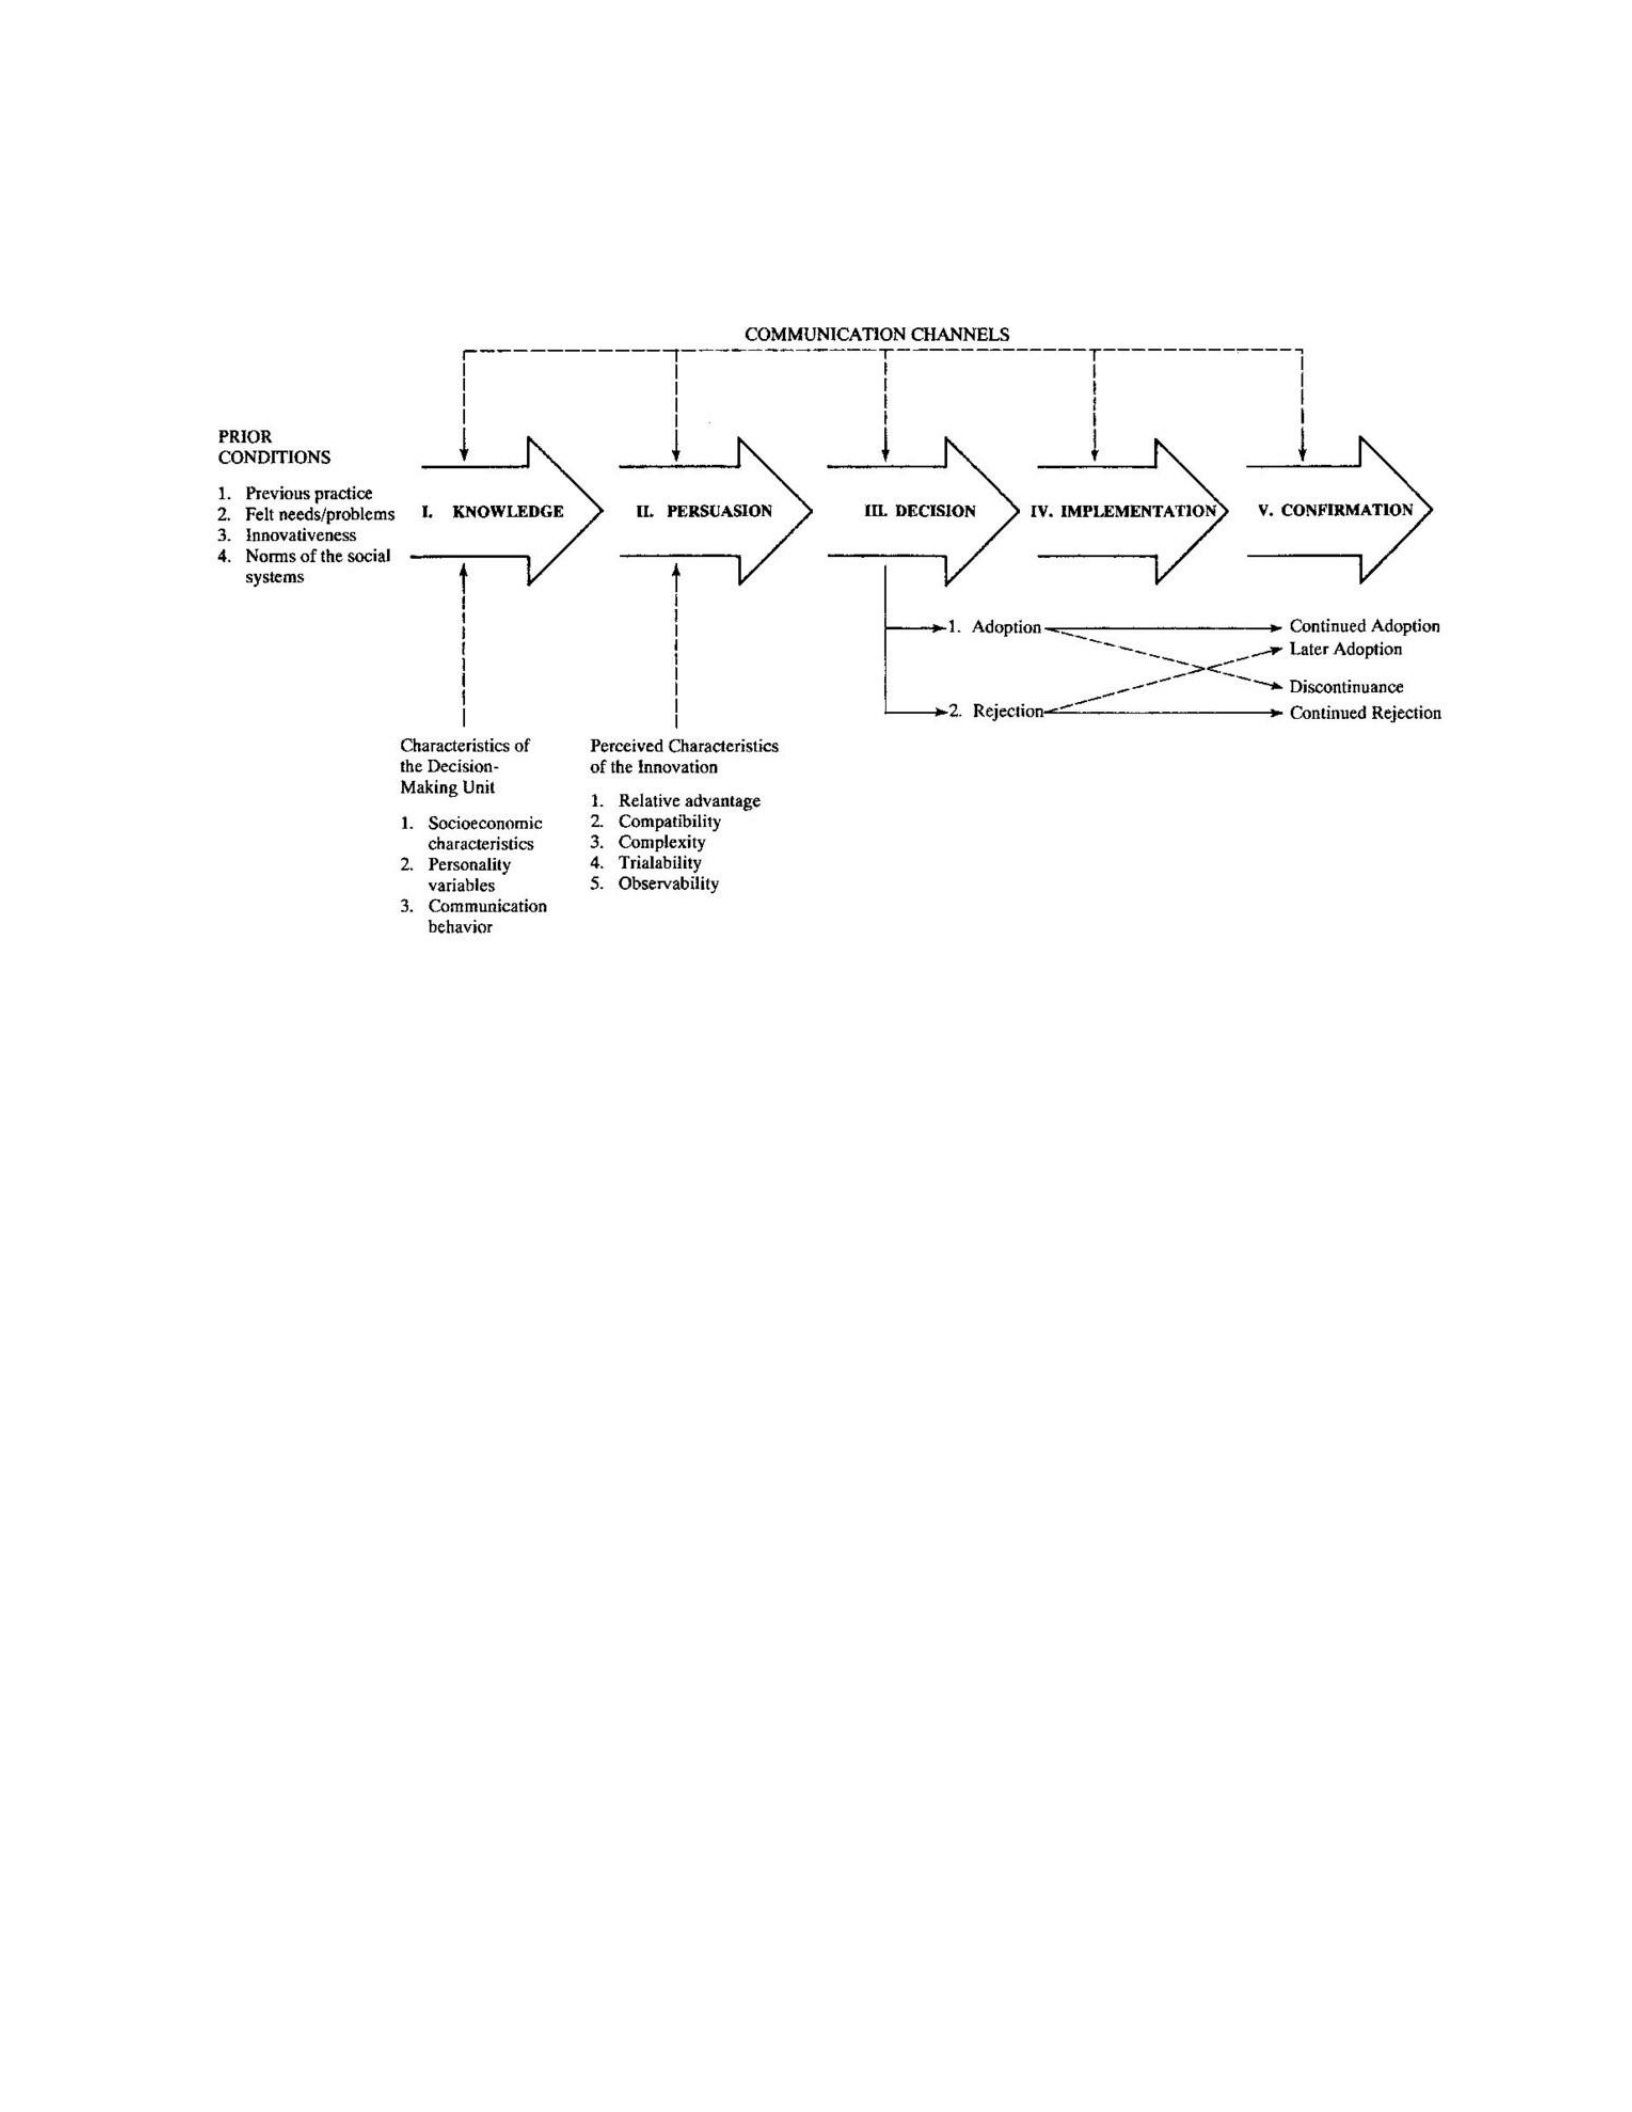
89
Figure 8
Rogers’ DOI Model.
A number of factors may have contributed to the inability to establish construct validity.
First, the hypothesized model was based on Rogers’ DOI model (see Figure 9); however, the
model was revised for this study. Revisions included adding confidence as a variable, based on
work by Calzone and colleagues (2012), and removing portions of the model that were not
evaluated by the GGNPS. Comparing Figures 8 and 9, note that social system was the only prior
condition included in this study. Also, communication channels, characteristics of a
decisionmaking unit, and perceived characteristics of the innovation were not included in this
study. As previously mentioned, this study also did not evaluate implementation or confirmation,
instead focusing on adoption of genetics/genomics as per the work of Calzone and colleagues
(2014).
The second factor potentially affecting the evaluation of construct validity is the
designation of some GGNPS items as the variables: confidence, competency/knowledge,
attitudes/receptivity, decision/adoption, and social systems. The EFA, discussed below,

90
demonstrated that a number of items originally intended to measure one variable were actually
more highly related to a different variable; for example, several items thought to be part of the
competency/knowledge variable were more closely related to the attitudes/receptivity variable.
The third and last factor to consider is that the content validity results indicated that some items
may not fit the concepts being evaluated and may be considered for revision or removal. The
content validity experts scored several items lowly and some of these items also performed
poorly on the EFA, highlighting the need to revise or remove them. Because EFA results shed
light on the main analyses, the results of the ancillary analysis are discussed first.
Ancillary Data Findings
The EFA was performed with five factors requested because the GGNPS contains five
variables: confidence, attitudes/receptivity, decision/adoption, competency/knowledge, and social
systems. Many items did not load on their GGNPS-designated variables. Confidence was the
only variable where items loaded as predicted. However, attitudes/receptivity, decision/adoption,
and competency/knowledge were identifiable variables, though some of items loaded
unexpectedly on other variables. Also, while the GGNPS identified competency/knowledge as
one variable, the EFA results indicated that these items loaded on two factors, both with the
central theme of competency/knowledge. In contrast, social systems items did not load on a
factor unique to social systems; some items did not load on any factors, some loaded on multiple
factors, and one item loaded on competency/knowledge.
Factor 1. (Confidence).
Anticipated loadings. All of the 14 items designated as confidence in the GGNPS loaded
onto Factor 1. All but one item demonstrated Thurstone’s simple structure and met loading
criteria (³ .30) (see Table 13). In fact, most items loaded above .70, with three items loading
above .90, demonstrating a strong relation of these items to the confidence variable. The one

91
exception was item P2_Q1_05 which asked nurses to rate their confidence in providing
emotional follow-up support after family history assessment. This item did load most strongly
on Factor 1 (.670) but also loaded .308 on Factor 2 (attitudes/receptivity).
As noted previously, Rogers (2003) did not include confidence in the DOI theory, but
Calzone and colleagues (2012) added confidence items to the GGNPS, an instrument created
based on the DOI theory, because they found that confidence plays an important role in the
adoption of genetics/genomics into nursing practice. This has been demonstrated empirically:
Calzone and colleagues (2012) reported that only 24% of nurses (n =38/159) were very or
somewhat confident when deciding what family history information is required to assess
susceptibility to common diseases. Similarly, Metcalfe and colleagues (2009) reported that only
3% (n = 3/100) of hospice nurses were confident enough to provide client education and only
20% (n = 20/100) were very confident in explaining the genetic basis of transmission for
Duchenne Muscular Dystrophy. Both articles noted that low confidence may adversely affect
adoption of genetics/genomics.
In a similar vein, Benner (1984) discussed confidence related to gaining clinical
expertise. Her research on confidence helped define the confidence variable related to nursing
practice. Benner reported that confidence increases the ability to manage multiple roles and
challenges. Calzone and Jenkins (2007) identified a number of roles and responsibilities for
nurses in adoption of genetics/genomics. The 14 GGNPS confidence items ask participants to
report their confidence in relation to use of family history information, patient education,
providing emotional support, discussing confidentiality of family history information, and
facilitating referrals for genetic services.
Unanticipated loadings. Two GGNPS-designated competency/knowledge items also
loaded ³ .30 on Factor 1 (confidence). The first item, P6_Q2_01: “Please rate your

92
understanding of the genetics of common diseases” (participants rated their knowledge as
excellent to poor) loaded .496 on Factor 4 (competency/knowledge 1); however, it also loaded
.445 on Factor 1 (confidence). This item may have loaded on two factors because participants
have to both consider how much they know about genetics/genomics and how they would rate
their level of knowledge. The second item P6_Q2_02, parallels the previous one: “In describing
your genetic/genomic knowledge, would you consider it to be...”. This item loaded .491 on
Factor 4 (competency/knowledge 1). It also loaded .445 on Factor 1 (confidence). Again,
participants may have considered both their knowledge and their confidence in their knowledge.
Factor 2. (Attitudes/Receptivity).
Anticipated loadings. Of the 17 GGNPS-designated attitude/receptivity items, only six
loaded on Factor 2 (attitudes/receptivity) (see Table 14). These six items pertained to potential
advantages of genetics/genomics. While these six items did demonstrate Thurstone’s simple
structure and loaded ³ .30, the loadings ranged from .306-.377. This indicates a relatively weak
relation of the items to the attitudes/receptivity variable.
Concerning the other 11 items, two items did not load above .30 on any factor and one
item was excluded from the EFA because it did not contain any variability, all participants
responded with the same answer. The remaining eight items designated as attitudes/receptivity
loaded on Factor 3 (decision/adoption). Unlike the six attitudes/receptivity items that pertained
to advantages, these eight items pertained to potential disadvantages of incorporating
genetics/genomics into nursing practice and are discussed in detail in Factor 3.
Unanticipated loadings. Unexpectedly, eight GGNPS-designated
competency/knowledge items also loaded onto Factor 2 (attitudes/receptivity). These items may
be more strongly related to attitudes/receptivity than competency/knowledge because they asked
participants if they thought there was genetic risk associated with specific clinical conditions

93
(e.g. colon cancer) and if nurses thought family history information should be collected for new
patients. Rogers (2003) describes the formation of an attitude as participants processing their
thoughts about an innovation and forming a favorable or unfavorable opinion regarding the
innovation.
Factor 3. (Decision/Adoption).
Anticipated loadings. Of the 12 GGNPS-designated decision/adoption items, eight
loaded onto Factor 3 (decision/adoption) (see Table 15). These eight items pertained to
limitations of using genetics/genomics, such as lack of time, lack of reimbursement, increased
liability, and limited expertise. The eight items loaded ³ .30 and demonstrated Thurstone’s
simple structure. The loadings varied between .363 - .606, indicating a moderately strong
relation to the decision/adoption variable.
Of the remaining four items, one did not load above .30 on any factor and three loaded on
Factor 4 (competency/knowledge 1). Those three items pertained to facilitating referrals to
genetic services and family history information; the items loaded ³ .30 and demonstrated
Thurstone’s simple structure for the competency/knowledge factor.
Unanticipated loadings. As noted above, eight GGNPS-designated attitude/receptivity
(Factor 2) items unexpectedly loaded on Factor 3 (decision/adoption). The items loaded ³ .30
and demonstrated Thurstone’s simple structure for the decision/adoption factor. These items may
be more strongly related to decision/adoption than attitudes/receptivity because they concern
potential disadvantages of incorporating genetics/genomics into nursing practice. The content of
the GGNPS asked about potential disadvantages of genetics/genomics such as: taking too much
time, lack of reimbursement, increased burden of responsibilities on nurses, and increased patient
anxiety. Moreover, these particular previously designated attitudes/receptivity items parallel the
items in the GGNPS that are designated as decision/adoption.

94
That is, items in Factor 3 parallel Rogers’ description of decision/adoption because
individuals are considering potential disadvantages and limitations of adopting an innovation;
they are considering whether it is the best course of action. This is further supported by Rogers’
(2003) definition of decision and adoption. Rogers defines decision as the thought process
leading up to choosing to adopt or reject an innovation. Adoption is use of an innovation because
it is “the best course of action available” (Rogers, 2003, p. 177).
Decision/adoption is an important variable to explore in the EFA because it is the ultimate
outcome variable in the hypothesized model and it is affected by a number of the other variables.
For example, Calzone and colleagues (2014) reported that genetics/genomics are not being fully
adopted into nursing practice. The authors cited several reasons for lack of adoption including
inadequate knowledge, a lack of understanding of the relevance, lack of confidence to translate
knowledge into adoption of genetics and genomics, and inadequate support from social
system(s).
Factors 4 and 5 (Competency/Knowledge 1 and 2). There were 25 total GGNPS items
designated by Calzone and colleagues (2014) as competency/knowledge. While the GGNPS
identified competency/knowledge as a single variable, both Factors 4 and 5 were identifiable as
competency/knowledge factors and are thus designated as competency/knowledge 1 and 2. This
indicates that more than one type of genetics/genomics knowledge may affect adoption.
Similarly, Rogers (2003) describes three different types of knowledge. Awareness-knowledge is
knowing an innovation exists. This is basic knowledge that may encourage individuals to gain
more insight into an innovation. How-to-knowledge is learning how to use an innovation.
Lastly, principles-knowledge is understanding how an innovation functions.
This interpretation is further supported by the fact that, as previously mentioned, eight of
the 25 GGNPS-designated competency/knowledge items loaded onto Factor 2

95
(attitudes/receptivity). These items do not pertain to any of the three types of knowledge defined
by Rogers. Rather, they ask if nurses thought there was genetic risk associated with specific
clinical conditions and if nurses thought family history information should be collected for new
patients. The focus on participants’ perceptions, what they thought, rather than type of
knowledge supports the items loading on Factor 2 (attitudes/receptivity). This left 17 items
expected to load on Factors 4 and 5.
Factor 4 (Competency/Knowledge 1).
Anticipated loadings. Of the 17 remaining GGNPS-designated competency/knowledge
items, seven loaded on Factor 4 (see Table 16). These items related to collection of family
history information. All seven items loaded ³ .30 and demonstrated Thurstone’s simple structure.
The loadings’ strength varied widely, ranging from .491-1.019. This may be related to the
variation among competency/knowledge questions; these seven items cover a variety of clinical
topics, including both understanding of genetics/genomics and how it is used in clinical practice.
Factor 4 items parallel Rogers’ (2003) notion of how-to-knowledge: they are related to collection
and use of family history information, using this information in clinical decision making, and
facilitating referrals for genetic services. This type of knowledge is essential to understanding
how nurses use genetics/genomics in clinical practice. Identifying these items using the EFA can
allow educators to create targeted learning initiatives to teach topics that are required to
understand and apply genetics/genomics in a clinical setting.
Unanticipated loadings. As previously discussed, two GGNPS-designated
competency/knowledge items that loaded on Factor 4 also loaded ³ .30 on Factor 1 (confidence).
Item P6_Q2_01 loaded .496 on Factor 4 (competency/knowledge 1) and .445 on Factor 1
(confidence). Item P6_Q2_02 loaded .491 on Factor 4 (competency/knowledge 1) and .445 on
Factor 1 (confidence).

96
In addition, three items pertaining to facilitating referrals to genetic services and family
history information loaded on Factor 4 (competency/knowledge 1) (.318-.401) even though they
were originally designated as Factor 3 (decision/adoption). This may be because the items
related to participants’ how-to- knowledge about how to collect and utilize family history
information. Lastly, one GGNPS-designated social system item also loaded onto Factor 4
(competency/knowledge 1) (.308); the item asked whether participants intended to learn more
about genetics. Perhaps participants interpreted this item as intent to gain more how-to
knowledge and thus it loaded on competency/knowledge.
Factor 5. (Competency/Knowledge 2).
Anticipated loadings. Out of 10 remaining GGNPS-designated competency/knowledge
items, six loaded on Factor 5; these items were related to clinical decision-making (see Table 16).
All six items loaded ³ .30 and demonstrated Thurstone’s simple structure. Similarly to Factor 4,
loadings varied significantly for Factor 5, ranging from .328-.912. The items from this factor
parallel principles-knowledge. Principles knowledge is not required to adopt an innovation,
according to Rogers (2003), but promotes understanding of how an innovation functions. Factor
5 items include knowing whether gender, race/ethnicity, genes, family history, and insurance
status are important to consider in clinical decision-making. Although Rogers theorizes that
principles-knowledge is not required for adoption, it can be used to help clarify and create a
context of how to use genetics/genomics in nursing practice.
Items that did not load. The remaining four competency/knowledge items did not load
above .30 on any factor and did not demonstrate Thurstone’s simple structure. The first item
asked if a family history of only first-degree relatives should be collected for all new patients.
This item may not have loaded because while family history information should be collected for
new patients, participants may have been uncertain of how many generations should be included.

97
The second item that did not load asked about the similarity of DNA between two unrelated
individuals. This item also had a low CVR (- .714), although this may be partly related to
misinterpretation of the question. One content expert stated that the similarity of genetic material
between two individuals was higher than the 90-95%, but that is the content that the question is
addressing. The answer to the question is ‘False,’ because the similarly of genetic material is
closer to 99.5% (Levy et al., 2007). The next item that did not load asked if a single gene variant
causes most common diseases. This item may not have loaded because participants were unsure
of the correct response or the term “variant” in relation to genetic information. The final item
that did not load asked if participants knew about The Essential Competencies and Curricula
Guidelines for Nurses in Genetics and Genomics. This item may not have loaded because it was
not related to a specific clinical topic; while important to address, this item asks about general
awareness of the competencies as opposed to specific genetics/genomics knowledge.
Social systems. Social systems did not load predominantly on a single factor. Of the five
social systems items, two did not load on any factors, two items loaded on multiple factors, and,
as noted, one item loaded on Factor 4 (competency/knowledge 1) (see Table 17). Rogers (2003)
considers diffusion of an innovation as a “kind of social change” (p. 6). New information is
diffused and adopted, leading to changes in the social system. Rogers adds that it may be
difficult to evaluate the role of the social system independently from the characteristics of the
individuals within that system. This illustrates how connected the social system is to the other
variables in the DOI model and parallels the results of the EFA. Social systems may be
pervasive throughout the other variables, as opposed to being an independent variable.
EFA discussion summary. The EFA results indicate that many items did not load on
their GGNPS-designated variables. However, the confidence variable did load as designated in
the GGNPS. In addition, although some item loadings varied, attitude/receptivity,

98
decision/adoption, and competency/knowledge were clearly identifiable variables in the EFA.
However, there were two distinguishable competency/knowledge factors instead of the
anticipated one. Lastly, social systems items either did not load consistently on an identifiable
factor, loaded on multiple factors, and one item loaded on Factor 4 (competency/knowledge 1).
Content Validity
Eight nursing experts were selected based on current employment, experience, and
evidence of scholarship in nursing and genetics/genomics. Experts with backgrounds in clinical
practice were selected, because the GGNPS is a tool assessing application of genetics/genomics
to clinical practice. Content validity experts rated items in the GGNPS from ‘not relevant’ to
‘very relevant.’ One participant responded as a learner, instead of as a content expert; her
response was excluded. The comprehensive CVI, computed as the mean of the content validity
ratios across all items, was 0.805. This exceeds 0.741, which Wilson and colleagues (2012)
identified as the required threshold when seven content experts evaluate an instrument.
Overall, content experts reported that the GGNPS has content validity. However, they
identified a number of items that were problematic and rated them lowly. Not surprisingly, many
of these problematic items were items that did not perform well on the EFA; loading on two
factors or having low loadings on a single factor. Thus, the results of content validity assessment
and the EFA support each other. The five items discussed below should be considered for
revision or removal.
The lowest CVR rated (- .714) item was a GGNPS-designated competency/knowledge
item P5_Q1: “The DNA sequences of two randomly selected healthy individuals of the same sex
are 90-95% identical”. In addition to having the lowest CVR, this item did not load above .30 on
any factor in the EFA and did not demonstrate Thurstone’s (1947) simple structure.

99
The next lowest CVR rating (.142) was given to a GGNPS-designated social systems
item P7_Q1_01: “Do you intend to learn more about genetics?” This item loaded on Factor 4
(competency/knowledge 1), with a loading of .308. The item discussed the intention to learn,
which may explain why it loaded on Factor 4 competency/knowledge 1 (how to knowledge).
However, the EFA loading was only slightly above the .30 threshold. One content expert
commented that this item may be misleading because most participants will feel obligated to
answer ‘yes’. To expand on her comment, participants may believe they should learn more about
genetics as health care providers and will answer ‘yes’ out of perceived obligation, as opposed to
intent to learn more about the topic.
Two items had a CVR rating of .428. A GGNPS-designated knowledge-competency item
P6_Q2_02: “In describing your genetic/genomic knowledge, would you consider it to be...”
(participants rated their knowledge as excellent to poor). One content expert noted that this item
may be redundant because the previous item (P6_Q2_01) asks participants to rate their
understanding of genetics of common diseases. The EFA supports this analysis; P6_Q2_01 and
P6_Q2_02 had similar loadings on Factor 4 (competency/knowledge 1) and Factor 1
(confidence). Both items loaded ³. 30 on two factors and had similar loadings for each factor.
Item P6_Q2_01 had a loading of .445 on Factor 1(confidence) and .496 on Factor 4
(competency/knowledge); item P6_Q2_02 had a loading of .445 on Factor 1(confidence) and
.491 on Factor 4 (competency/knowledge 1). Based on these findings, items P6_Q2_01 and
P6_02_02 may be merged into one item focusing on participants’ genetic/genomic knowledge.
The other item with a CVR of .428 was a GGNPS-designated confidence item
P2_Q1_12: “Give patients information about the limitations of genetic testing for common
diseases.” However, this item loaded strongly (.931) on Factor 1 (confidence). One content
expert explained why the item was poorly rated in the CVR, stating providing this information

100
may be outside of the scope of practice of nursing. Instead, nurses would reinforce information
provided by genetics specialists and provide clarification.
One additional item, included in content analysis, was not a part of the GGNPS used in
this study. Rather it was added when the GGNPS was edited after pilot testing. This item also
had a low CVR rating of .428. This item: “Thinking about how you support clinical decisions
(such as administering drugs prescribed), how important do you think each of the following is to
consider? Genetic Test Result,” while asking about very important content, is complex. Some
content reviewers were unsure if the item was asking about medication administration
specifically or medication administration was just one example of a clinical decision. Genetic
testing results may be considered when administering a number of medications, such as codeine
and warfarin (Kitzmiller, Groen, Phelps, & Sadee, 2011). However, the question seems to be
asking about general clinical decision-making. One content reviewer provided helpful insight,
stating an example may clarify this item.
In summary, while many items had very high CVR’s, the content experts identified a
number of items that may be unclear or may be misinterpreted by individuals completing the
GGNPS. Content validity results also shed light on why construct validity could not be
established. Several items that were scored lowly by content experts also performed poorly on
the EFA. Items with low CVRs that also loaded on multiple factors in the EFA could have
affected the results of a CFA because the item(s) likely attempted to load on multiple factors,
increasing the likelihood that parameter estimates could not be provided by MPLUS. Items that
scored lowly and did not load on any factor in the EFA could affect the SEM and CFA; making it
more difficult to identify the factors in the model and the relations between them. Content expert
analysis also provides direction for future assessments of construct validity. Items that
performed poorly can be considered for revision or even removal from the instrument.

101
Following this evaluation, the CFA and SEM can be reassessed.
Face Validity
Face validity was conducted, with seven reviewers, to evaluate the ease of understanding
and relevance of the GGNPS to nursing practice. All reviewers were currently practicing nurses
with a variety of educational and clinical backgrounds. None of the reviewers had specific
education or experience in genetics/genomics; they were purposely selected to provide the
perspective of the majority of nurses in the workforce.
Five of the seven reviewers reported the GGNPS was somewhat clear/easy to understand;
the remaining two reviewers reported that it was very clear/easy to understand (see Table 7).
The majority of reviewers (n = 5/7) also reported the GGNPS items were pertinent to their
clinical practice, while two reviewers reported that they were not relevant. However, among the
two face validity reviewers who reported that the GGNPS was not pertinent to their clinical
practice, one reported that it was very clear/easy to understand. There was not a clear pattern
among reviewers of understanding the content of the GGNPS and realizing that
genetics/genomics applies to nurses across all specialties and practice settings. This indicates a
knowledge gap regarding the use of genetics/genomics in clinical practice. In fact, four out of
seven face validity reviewers reported that they did not use genetics/genomics in their clinical
practice, while three out seven reported that they did (see Table 7).
Overall feedback from the reviewers indicated that the GGNPS has face validity. None of
the participants reported that the GGNPS was ‘not very clear’ or ‘unclear and difficult to
understand.’ In addition, five out of seven nurses from a variety of clinical specialties, roles,
educational backgrounds, and levels of experience reported that the GGNPS was pertinent to
their clinical practice. One of the goals of this instrument is to make it applicable for a variety of
nurses, regardless of specialty, clinical role, or level of education (Calzone et al., 2014).

102
Construct Validity
As noted, construct validity could not be established because the CFA failed to converge.
Furthermore, the SEM showed that the hypothesized model did not fit the data and many
relations in the SEM were weak in light of the large sample size. Please note, standardized units
of measurement for the SEM are discussed in Appendix G; this information is presented in the
appendix because β weights for nominal and ordinal data are complex and require an extended
discussion.
Confirmatory factor analysis (CFA). A CFA, using the original data and imputed data,
was conducted to evaluate whether the GGNPS items comprised the underlying variables of
confidence, competency/knowledge, attitudes/receptivity, decision/adoption, and social systems.
After over 34 hours and 460 iterations, MPLUS reported that the models did not converge on a
stable set of parameter estimates. This occurred because the hypothesized GGNPS variables
mentioned above did not fit the data. The items from the GGNPS that were thought to make up
the variables of confidence, competency/knowledge, attitudes/receptivity, decision/adoption and
social systems could not be grouped this way despite multiple attempts by the statistical
software. As discussed, EFA provided further evidence of this because items that were thought to
load on one factor, frequently loaded on another factor.
As a result, no factor loading can be discussed. This highlighted the need to conduct an
EFA in the ancillary analysis. A five-factor model was selected to parallel Rogers’ (2003) DOI
model and the EFA produced a data-driven analysis of how each item from the GGNPS loaded
on the factors. EFA results indicated that GGNPS-designated confidence items loaded on one
factor; however, GGNPS-designated competency/knowledge, attitudes/receptivity, and
decision/adoption items were more interrelated than originally thought. While
competency/knowledge, attitudes/receptivity, and decision/adoption were identified as variables
following the EFA analysis, some items thought to be associated with one variable actually

103
loaded on a different variable. By contrast, social system was not an identifiable variable;
GGNPS-designated social systems items either did not load on any factors, loaded on multiple
factors, and one item loaded on competency/knowledge.
Structural equation model (SEM). A SEM was used to explore overall model fit and
the relations among the variables in the data. Evaluation of a number of overall fit parameters
(Chi-square, RMSEA, CFI, and BIC) all indicated that the study’s hypothesized model did not fit
the data. The poor fit was consistent in both the original data set and all four imputations.
Further supporting the poor fit is the significant amount of variance (residual) that was not
explained (see Table 10). The unexplained variance may be due to relations among variables that
were not considered in the hypothesized model. The poor fit of the data to the hypothesized
model, based on work by Calzone and colleagues (2012), combined with the large amount of
unexplained variance, again illustrated the need to conduct an EFA in ancillary analysis. The
EFA can help increase understanding of both the variables themselves and can be used to
examine proposed relations between the variables.
Figure 9
p* < 0.001; p** = 0.013
SEM Using the Original Data Set.
0.104*
Social Systems
Competency
/Knowledge
Attitudes/Receptivity
Decision/Adoption
0
.391*
0.150*
0.717*
0.399
*
Confidence
-
0.039**
-
0.225*

104
Not only did the data not fit the hypothesized model, many of the relations among the
variables in the SEM were weak. Because a large sample size increases the likelihood that
statistically significant correlations exist among the data, the SEM results must be carefully
evaluated (Wolf, Harrington, Clark, & Miller, 2013). The weak relations may be partly due to
conceptual issues. That is, the hypothesized model above was based on Rogers’ DOI model, but
it was revised for this study to include confidence as a variable and exclude components of the
DOI that were not measured in the GGNPS. The weak relations may also be explained in part by
the EFA. The EFA showed that many items designated in the GGNPS as one variable, actually
loaded on a different variable. Even if a small number of items in each variable, other than
confidence, actually measured a different variable this would create measurement error. This
measurement error would then be compounded because the SEM evaluated direct and indirect
relations amongst the five variables.
Competency/knowledge on attitudes/receptivity. An example of a statistically
significant, but weak, relation is the direct effect of competency/knowledge on
attitudes/receptivity (.104, p < 0.001) (see Figure 10). This is a surprising finding because
according to Carroll and colleagues (2009) increasing knowledge has a positive effect on
attitudes/receptivity. Researchers conducted an educational intervention that positively affected
the attitudes about genetic testing of participants including nurses, nurse practitioners,
physicians, and other health care providers. Following an educational workshop and modules,
researchers reported a statistically significant increase in the number of participants agreeing that
genetic testing was beneficial in the management of adult-onset diseases (p= .031), using the
McNemar test for matched categorical variables (Carroll et al., 2009).
A number of factors may explain this surprising finding. According to Rogers (2003),
while knowledge is predominantly 'knowing' or cognitive, attitude/receptivity is predominantly

105
'feeling'. Rogers adds that attitude is “a relatively enduring organization of an individual’s
beliefs about an object that predisposes his or her actions” p. 174-175. For example, if an
individual associates use of genetics/genomics in their clinical role with stress or uncertainty,
increased knowledge will not fully overturn this enduring attitude. In fact, results show that the
hypothesized model was not correct, increased knowledge has little effect on one’s attitude.
The weak relation may be partially attributed to the EFA results as well. A number of
GGNPS-designated attitudes/receptivity items loaded on decision/adoption; these items may
have created measurement error. Items that were actually more related to the decision/adoption
variable were evaluated in the SEM as part of the attitudes/receptivity variable, impacting the
model’s ability to show accurate relations between variables.
Results of reliability testing should also be considered in assessing relations between the
variables. A number of attitude/receptivity items, especially items that were “check all that
apply” or included large Likert scales were the most poorly performing items during reliability
evaluation (Calzone et al., 2016). The low reliability of these items led researchers to revise or
eliminate a number of those questions. Therefore, relations that include attitude/receptivity items
should be evaluated with the knowledge that a number of attitude/receptivity items performed
poorly during reliability testing and were amended or eliminated as a result.
Competency/knowledge on confidence. The direct effect of competency/knowledge on
confidence in using genetics/genomics in one’s practice was a stronger (.399, p < 0.001) relation,
meaning increased knowledge about genetics/genomics increased confidence (see Figure 10).
This relation is supported by Benner (1984), who noted that experienced (knowledgeable) nurses
have more confidence in their abilities and are more capable of managing difficulties and
challenges. As nurses gain knowledge and increase their mastery of content, they increase their
critical thinking ability. Critical thinkers, therefore, exhibit a number of characteristics including

106
confidence (Benner et al., 2008). Thus, it is plausible that nurses who have more knowledge of
genetics/genomics are more confident in the use of this knowledge.
This relation was also supported empirically; Silva and colleagues (2016) evaluated the
effect of knowledge on confidence. Study participants completed an educational program about
suicide risk assessment and management. Participants consisted of 2,843 nurses, physicians,
case managers, administrators, and support staff. Those who completed the educational training
had statistically significantly higher confidence in their ability to assess patients and provide
interventions than those who did not receive the training (F [1,1333] = 298.21). This supports
the results of the hypothesized SEM model, which found a substantial relation between
competency/knowledge and confidence.
As previously noted, items in the GGNPS that Calzone and colleagues (2012) designated
as part of the confidence variable, all loaded strongly on the confidence factor. Thus, it is likely
that these items accurately measure confidence. Potential measurement error may have resulted
from GGNPS-designated competency/knowledge items that loaded on Factor 2
(attitudes/receptivity) in the EFA. According to the EFA results, those items were more related to
the attitudes/receptivity variable as opposed to the competency/knowledge variable; as a result,
they may have impacted the strength of this relation.
Competency/knowledge on decision/adoption. The indirect effect of
competency/knowledge on decision/adoption (-.023), through attitudes/receptivity, (not shown in
diagram see Table 11) was negative, weak. As described by Rogers (2003), diffusion of
innovation is a process whereby an individual initially acquires knowledge about an innovation
and forms a favorable or unfavorable attitude about the innovation. This is the direct effect of
knowledge on attitudes/receptivity discussed above. After attitudes are formed as a result of this
knowledge, the person decides to adopt or reject it.

107
However, in a clinical setting/context, additional factors may influence adoption, such as
limited time/resources and competing responsibilities. A previously described study supports this
point. Cook and colleagues (2013) evaluated the effect of an educational intervention on the
knowledge, attitudes, confidence, and clinical practice of nurses providing care for patients with
mild traumatic brain injury (mTBI). Following the educational intervention about new clinical
guidelines, trauma nurses reported being more able to identify interventions to alleviate
symptoms following an mTBI (χ² = 6.125, p = .001)(Cook et al., 2013). Upon assessing nurses’
attitudes, 96% (n = 24/25) of participants reported the educational intervention (knowledge)
increased their understanding of symptom assessment and new clinical guidelines. However,
while between-group analysis showed that some nurses increased their use of mTBI symptom
assessment (50-86%), only 52% of the participants reported using mTBI symptom assessment in
their clinical practice (adoption) (Cook et al., 2013). Additional factors, such as social systems,
that relate to nurses’ responsibilities and work stressors may affect the indirect relation of
competency/knowledge and decision/adoption, through attitudes/receptivity.
Finally, the EFA results indicated that competency/knowledge loaded on three factors and
three GGNPS-designated decision/adoption items loaded on Factor 4
(competency/knowledge 1), this measurement error may partially account for the weak relation
between the two variables.
Attitudes/receptivity on decision/adoption. In fact, the direct negative effect of
attitudes/receptivity on decision/adoption was stronger and statistically significant (-.225, p <
0.001) (see Figure 10). Although this is a surprising finding, Rogers (2003) states that one’s
attitude or receptivity to an innovation is enduring. GGNPS-designated attitude/receptivity items
ask nurses about the perceived advantages and disadvantages of genetics/genomics. This effect

108
may indicate that perceived disadvantages have a substantial negative effect on the decision to
adopt genetics/genomics into nursing practice.
Examples of disadvantages evaluated in the GGNPS include genetics/genomics taking too
much time and being an additional burden for nurses. Nursing literature often sites a lack of time
and overwhelming burden of responsibilities as a challenge for nurses in many clinical practice
settings (Sussner et al., 2011; Tourangeau et al., 2013). The perceived disadvantages of
genetics/genomics can lead to negative attitudes/receptivity toward the innovation and have a
negative effect on its adoption. To promote adoption of genetics/genomics, clinical agencies
must promote positive attitudes about this innovation; however, this must be done in context of
health care institutions providing support for nurses. This support may include addressing
workplace stressors and creating support networks to promote education and best-practice
initiatives. This also demonstrates the pervasiveness of the social system variable. The role of
health care organizations is further discussed below when evaluating the relation between
attitudes/receptivity and social systems.
However, as previously mentioned, a number of attitude/receptivity items performed
poorly during reliability evaluation and were amended or eliminated as a result. Therefore,
relations that include attitude/receptivity items should be evaluated with the knowledge that both
the poor performance of these items during reliability testing and their revision could affect the
relation between attitudes/receptivity and decision/adoption.
This relation must be cautiously interpreted, eight out of 17 GGNPS-designated
attitudes/receptivity items loaded on Factor 3 (decision/adoption) (see Table 14). Since so many
items that were thought to represent the attitudes/receptivity variable actually loaded on
decision/adoption, this increases the risk of measurement error and the relation between these
two variables should be reevaluated after reclassifying the variables based on the EFA results.

109
Social systems on competency/knowledge. The direct effect of social systems on
competency/knowledge (.717, p < 0.001) was statistically significant and strong (see Figure 10).
This supports Rogers (2003) assumption that diffusion of innovations is a process that is
encompassed within a social system; diffusion of innovations is “communicated through certain
channels over time among members of a social system” (p. 5). He also summarizes the diffusion
of innovations process as essentially an “information-seeking and information-processing
activity” (Rogers, 2003, p. 172). In fact, knowledge is the first step of the diffusion of
innovations process and has indirect effects on all of the following steps. As a result, both social
systems and knowledge are strongly integrated throughout the DOI process.
An example of the effect of social systems on competency/knowledge is demonstrated in
the nursing faculty champion initiative study (Jenkins & Calzone, 2014). Acquisition of
genetics/genomics knowledge required not only faculty expertise, but support from university
administrators and peer networks. University deans and program directors championed faculty
applicants to participate in the initiative and peer support networks provided an additional source
of social system support by using faculty genetics/genomics experts as resources for learners.
Results of the initiative indicate that the faculty champion model was effective in promoting
integration of genetics/genomics in nursing curricula; however, researchers did note a need for
additional communication with participants to maintain engagement. Initiatives such as the
faculty champion program can be important mechanisms to help faculty reach the educational
genetics/genomics-related goals outlined by the ACCN and CCNE.
The EFA results provide a caveat when interpreting the relation between social systems
and competency/knowledge. Three out of five GGNPS-designated social system items loaded on
other factors and two did not load on any factor. In addition, GGNPS-designated
competency/knowledge items loaded on three factors in the EFA. The strength of the relation

110
reported here does not include additional insights provided by the EFA. In fact, all of the
relations including social systems require further exploration because the majority of
GGNPdesignated social system items loaded on different factors. Further studies are required to
amend the GGNPS and reevaluate the relations among the variables.
Social systems on attitudes/receptivity. In contrast, the direct effect of social systems on
attitudes/receptivity (.150, p < 0.001) was much weaker, although statistically significant (see
Figure 10). Indicating that support from the social system has a smaller than anticipated role in
promoting a positive attitude towards genetics/genomics. This is an unexpected finding since
Rogers (2003) describes both the pervasive nature of social systems and how one’s attitudes
toward an innovation are relatively enduring. This relation requires further exploration in future
research, because in the EFA, a number of attitude/receptivity items loaded on factors other than
the GGNPS-designated attitude/receptivity variable. In addition, GGNPS-designated social
systems items loaded on a variety of factors. This relation also requires further exploration
because a number of attitude/receptivity items performed poorly during reliability testing and
were amended or eliminated as a result.
The relationship between social systems and attitudes/receptivity may be weak due to the
social climate in the workplace and how it affects nurses’ attitudes/receptivity to innovations.
Nurses often receive mixed messages, on one hand current and patient-centered clinical practice
are emphasized, but in reality nurses are pressured to prioritize responsibilities emphasized by
the clinical institutions. For example, medication administration within a specific time frame.
Tourangeau and colleagues (2013) described inadequate time and poor staffing as frequent
nursing stressors. Not only are nurses are required to administer medications and answer call
bells in a timely manner, but they are often caring for a high patient load. In addition,
benchmarks such as patient satisfaction are continuously monitored by instutions. Health care

111
organizations prioritize measures such as patient satisfaction, evaluated in the HCAHPS survey,
partially because it determines reimbursement of over $850 million dollars annually (Zusman,
2012). The reality of nursing is that nurses are often faced with a high patient load and numerous
time pressures, while still being encouraged to maintain a current clinical practice that reflects
innovations such as genetics/genomics. While many nurses may strive to maintain a clinically
current practice, stressors from the social system of the health care organization are likely to
cause ambivalnce regarding complex innovations such as genetics and genomics. This is further
emphasized by results of the MINC study, in which 25.3% (n = 1,342/5,314) of participants
reported they believed senior staff members considered genetics an important part of the
participants’ role. Genetics/genomics may compete with other responsibilities and do not
directly affect reimbursement for RNs, thus resulting in the weak relation between social systems
and attitudes/receptivity.
Social systems on decision/adoption. While the direct effect of social systems on
decision/adoption was relatively strong (.391, p < 0.001) (see Figure 10), the indirect relation
between social systems and decision/adoption (-.034) was a negative and weak relation (see
Table 11). That is, social system support does promote adoption of genetics/genomics by nurses.
However, social system support, as an indirect relation through attitudes/receptivity, does not
contribute to adoption of genetics/genomics. Rogers (2003) describes diffusion of innovations as
a process encompassed within the social system. He also adds that norms of the social system
establish patterns of behavior among its members. Therefore, the relation between social
systems and decision/adoption is expected to be strong. The indirect relation through
attitudes/receptivity is expected to be weak because the relation between social systems and
attitudes/receptivity was also weak.

112
This is seen clinically in a study by Shields and colleagues (2010). The authors
highlighted that social system factors may prevent correct diagnosis of maturity onset diabetes of
the young (MODY). Geographical areas with greater research interest in MODY have higher
rates of diagnosis and referral. Social systems in those health care organizations may provide
additional support because research interests bolster vigilant clinical screening for conditions
such as MODY. The weakness of the indirect relation observed in this study may be due to the
moderating effect of attitudes/receptivity. Nurses' attitudes/receptivity are often related to the
perception of the innovation as related to competing work demands and stressors. For example,
nurses report inadequate time as a major barrier to collecting family history information, further
demonstrating that high workload and inadequate time are perceived disadvantages of
genetics/genomics (Sussner et al., 2011). A study using Rogers' DOI, although unrelated to
genetics/genomics, also identified time pressures perceived by nurses (Lee, 2004): there, the DOI
model was used to evaluate nurses’ perceptions of the innovation of computerized care systems.
Time shortage as a stressor was identified as a key theme. This stressor negatively affected
nurses’ attitudes toward the innovation.
However, similarly to other relations including social systems, it is important to consider
that EFA results indicated the GGNPS-designated social system items loaded on a variety of
other factors and some GGNPS-designated decision/adoption items loaded on
competency/knowledge. The relations must be reevaluated in further studies.
Confidence on attitudes/receptivity. The direct effect of confidence on
attitudes/receptivity (.039, p = 0.013) was the weakest relation in the SEM and was not
statistically significant in imputed data set 1 (see Figure 10 and Appendices F.1-F.4). This
indicates that confidence does little to create a positive attitude or increase receptivity towards
genetics/genomics; it is an anticipated finding because confidence has a weak effect on creating a

113
positive attitude towards genetics/genomics. This could be related to other variables affecting the
relation between confidence and attitudes/receptivity. For example, Metcalfe and colleagues
(2009) evaluated the confidence and attitudes of hospice nurses in their use of genetics in nursing
practice. Initially the attitude of 43% (n = 43/100) of nurses was that adopting genetics into
hospice care was of ‘little importance’; only 3% (n = 3/100) were confident enough to teach
clients. However, after reading scenarios about applications of genetics in hospice care, 66- 99%
rated genetics as ‘very important’ or ‘essential’ (Metcalfe et al., 2009). A key consideration in
this study is that knowledge may have also affected nurses’ attitudes; the intervention that
increased nurses’ attitudes/receptivity included education about genetic/genomic applications.
This provides insight into the weak relation between confidence and attitudes/receptivity seen in
this study; the weak relation between confidence and attitudes/receptivity may also be affected
by additional variables, such as competency/knowledge.
The EFA results also help explain the weak relation between confidence and
attitudes/receptivity. Although GGNPS-designated confidence items loaded consistently on
Factor 1, eight out of 17 GGNPS-designated attitudes/receptivity items actually loaded on Factor 3
(decision/adoption). As a result, the SEM may not accurately evaluate the relation between
confidence and attitudes/receptivity.
In addition, as previously mentioned, a number of attitude/receptivity items performed
poorly during reliability evaluation and were amended or eliminated as a result. Therefore,
relations that include attitude/receptivity items should be evaluated knowing that both the poor
performance of these items during reliability testing and their revision could affect the relation
between attitudes/receptivity and confidence.
Confidence on decision/adoption. The indirect effect of confidence on decision/adoption
(.0008) is the weakest indirect relation in the SEM (see Table 11). That is, confidence, through

114
attitudes/receptivity, has very little effect on the decision to adopt genetics/genomics into nursing
practice. Confidence is not an explicit part of the DOI model; however, Rogers (2003) does
address how personality aspects can affect adoption of an innovation. He describes earlier
adopters as better able to cope with uncertainty and risk. Benner’s (1984) research regarding
confidence paralleled Rogers’ views; she noted experienced nurses have more confidence in their
abilities and are better capable of managing difficulties/challenges.
However, this is a surprising finding because multiple studies have found a relationship
between confidence and decision/adoption. Barr and McConkey (2006) noted that low
confidence affected adoption of genetics/genomics by nurses and midwives. The study defined
adoption as providing referrals and patient education. Only 2.5% (n = 5/194) strongly agreed
and 10.8% (n = 21/194) agreed that they were comfortable referring clients to a genetic
counselor; 1.5% (n = 3/194) strongly agreed and 7.2% (n = 14/194) agreed that they were
comfortable discussing test results of pediatric patients. This was supported by findings by
Bottorff and colleagues (2005) who reported that decreased confidence was associated with
decreased adoption of genetics/genomics by nurses (n = 975); researchers defined adoption as
providing referrals, gathering genetic information, and obtaining informed consent for releasing
genetic testing information.
This surprising finding may be partially explained by the fact that the indirect relation
between confidence and decision/adoption could be affected by attitudes/receptivity. Negative or
mixed attitudes/receptivity towards genetics/genomics could affect adoption even if individuals
increase their confidence. In addition, a number of items originally designated as
attitudes/receptivity and decision/adoption in the GGNPS did not load on these variables in the
EFA. The relation between confidence and decision/adoption should be further explored in

115
future research that will reevaluate a CFA and SEM, following modifications based on EFA
results.
EFA results similarly help to explain the weak relation between confidence and
decision/adoption. The GGNPS-designated confidence items loaded consistently on Factor 1,
but three out of 12 GGNPS-designated decision/adoption items loaded onto Factor 4
(competency/knowledge 1) (see Table 15). In addition, the indirect effect of confidence on
decision/adoption is through attitudes/receptivity. Eight out of 17 GGNPS-designated
attitudes/receptivity items actually loaded on Factor 3 (decision/adoption). The measurement
error in each variable may be compounded as the relation between variables is evaluated.
Additional Considerations
There are two additional considerations in evaluating the SEM results. First, as
previously mentioned, the test-retest reliability analysis conducted by Calzone and colleagues
(2016) resulted in edits to several attitude/receptivity questions, because they were some of the
worst performing items in the reliability analysis. The SEM results of this study also demonstrate
that attitude/receptivity items contributed to the weakest relationships in this analysis. Evaluation
of Figure 9 demonstrates that variables endogenous and exogenous to attitudes/receptivity were the
weakest relationships in the SEM. Examples include the relationship between
competency/knowledge and attitudes receptivity (.104); attitudes/receptivity and decision/adoption
(-.225); confidence and attitudes/receptivity (-.039) and social systems and attitude receptivity
(.150). Relations that included attitudes/receptivity as either the dependent or independent variable
were all weaker than relations that looked at variables other than attitudes/receptivity.
By contrast, the SEM results support the strength of the effect of social systems.
Although the results of the EFA demonstrate that social system items did not load as a cohesive
variable, evidenced by most social system items either not loading above .30 on a variable or

116
loading on multiple variables, social system items account for two strong relationships within the
SEM. Specifically, the relationships of social systems and competency/knowledge (.717) and
social systems and decision/adoption (.391). In the SEM analysis, each variable was evaluated
using a factor score based on the GGNPS-designation. For example, the social system factor
score was determined by combining the participants’ responses to the GGNPS-designated social
system items. GGNPS-designation was used for all variables in the SEM because it was based
on previous research by Calzone and colleagues (2012, 2014), based on their analysis of Rogers’
DOI theory and evaluation of the Essential Competencies and Curricula Guidelines for Nurses in
Genetics and Genomics. The strength of relations in the SEM that include social systems,
compared to the weak performance of the social system items in the EFA, indicate that although
social systems may not be a standalone variable, social system items do explain a significant
portion of variance in the analysis and play an important role in understanding the relationships
between the variables. In further studies, social systems may be explored as a moderating factor
or social system items can be evaluated individually, as opposed to as a cohesive variable.
Summary Analyses support that the GGNPS has both content and face validity. However,
construct validity remains to be established. This study’s proposed CFA and SEM models did
not fit the data. EFA results, in ancillary analysis, shed light on likely sources of measurement
error and provide the basis for recommendations concerning revision and retesting of the
GGNPS.

117
Chapter VI
Conclusions, Implications, and Recommendations
Findings from this study met the threshold for both content and face validity for the
GGNPS. Although construct validity could not be established, the findings provide insights that
can guide future evaluation of construct validity. This chapter discusses conclusions and
implications for nursing practice, research, and education. It also addresses limitations of the
study and goals of future research.
Conclusions
Content validity. The comprehensive CVI, computed as the mean of the content validity
ratios across all items, met the threshold required to establish content validity. However, the
content experts identified a number of items in the GGNPS that may require revision. In fact,
many of these same items did not perform well in the EFA. Information from the content
validity analysis and the corroborating EFA results can be used to reevaluate those items.
Furthermore, this information can be used in future analyses of construct validity of the GGNPS.
Face validity. Findings from this study also support that the GGNPS has face validity.
Face validity was established by evaluation of the GGNPS for ease of understanding and
relevance to nursing practice.

118
Construct validity. The results of this study cannot establish construct validity based on
the CFA and SEM results. The hypothesized model could not converge on a stable set of
parameter estimates and the CFA did not produce factor loadings. This occurred because the
GGNPS-designated confidence, competency/knowledge, attitudes/receptivity, decision/adoption,
and social systems items did not load on those corresponding variables. The EFA provided
further evidence of this because many items that were designated as one factor loaded on another
factor. Additionally, the SEM results indicated that the hypothesized DOI model did not fit the
data, and many relations in the SEM were weak in light of the large sample size.
Ancillary analysis. The EFA provided significant insight into this study’s main analyses.
While confidence items loaded as predicted in the EFA, multiple items in the
attitudes/receptivity, competency/knowledge, and decision/adoption variables unexpectedly
loaded on other variables. In addition, consistent with Rogers’ DOI theory of different types of
learning related to adoption of innovations, competency/knowledge loaded on two factors.
Lastly, social systems did not load on a unique factor. Instead, some items loaded on multiple
factors, some did not load on any factors, and one item loaded on competency/knowledge.
The implications of the EFA findings are further discussed below as implications for future
research on the GGNPS.
Limitations
Several limitations must be noted when considering this study’s failure to establish
construct validity including: hypothesis of an incomplete SEM model, subject burden, and data
missingness.
Incomplete SEM model. The use of a SEM to establish construct validity was limited
because the GGNPS does not purport to measure several components of Rogers’ DOI model.
Specifically, the GGNPS does not measure prior conditions, other than social systems, that may

119
affect adoption of new innovations. According to Rogers (2003), prior conditions also include
previous practice, felt needs/problems, and innovativeness.
The GGNPS also does not measure characteristics of a decision-making unit, as described
by Rogers (2003), and their potential effect on adoption of genetics/genomics. These
characteristics include socioeconomic characteristics, personality variables, and communication
behavior. Socioeconomic characteristics related to adoption of genetics/genomics may include
the ability to fund nursing education (e.g. continuing on to a baccalaureate or master’s degree)
and/or means to purchase continuing education courses. Rogers (2003) reports that personality
variables are studied less often partly because it is difficult to measure aspects of someone's
personality. However, these variables can affect the rate of adopting an innovation. Rogers gives
examples of the personality traits that promote early adoption include being open to new ideas,
having greater ability to think abstractly, having a favorable attitude towards change, being able
to cope with uncertainty and risk, and having a positive attitude towards scientific research.
Based on the DOI model, communication behavior also affects adoption of innovations.
According to Rogers, early adopters are more connected to members of their social systems, seek
information more actively, and have greater knowledge regarding innovations.
At present, the GGNPS does not include items that evaluate the characteristics of a
decision-making unit or prior conditions. The GGNPS contains 72 items and demographic
questions; therefore, adding items may make the instrument too long and cumbersome to
complete. Instead, as discussed below in future analyses, additional insights into characteristics
of decision-making units and prior conditions can be gathered via focused studies. For example,
qualitative analyses highlighting these portions of Rogers’ theory.
However, it is important to mention that the GGNPS was shortened following reliability
testing. Poorly performing items were reformatted or, if other, better performing items, measured

120
the same domain, the poorly performing item was eliminated (Calzone et al., 2016). Items from
three “check all that apply” questions were eliminated, those items were part of the
attitudes/receptivity domain. Four confidence items were eliminated. A component of one
decision/adoption item was eliminated. A competency/knowledge item discussing the genetic
risk of lung cancer was removed. Lastly, two questions, one addressing the preferred format for
continuing education and one about how family history is collected were deleted and therefore
not mapped to domains. Therefore, if focused studies about decision-making units or prior
conditions yielded significant insights, that content could be considered for addition to the
GGNPS.
Subject burden. Survey burden and time constraints are common, but important,
limitations in clinical research. RNs may have completed the GGNPS during a busy shift and
had inadequate time to consider all of the items carefully. Some may intend to participate but
realize they do not have adequate time, others may feel pressured by management to participate
and do not answer to the best of their ability. Of the total 7,798 participants, 679 (8.71%)
respondents opened the instrument to complete it but left all items blank. In addition, 100% of
the institutions used for data collection were concerned with survey burden and had conducted
institution-wide nursing data collection in the past six months (Calzone et al., 2014). Thus, the
accuracy of responses may have added to measurement error.
Missing data. The data set contained a substantial amount of missing responses.
Welch’s two-sample independent t-tests were used to determine if data could be considered
missing at random (MAR). Missingness on decision/adoption items could not be considered to
be MAR; however, missingness on other variables did appear to be MAR. As a result, because
all data are not MAR, multiple imputation was used to account for missing items. Multiple
imputation replaces missing data with values imputed from the values of all existing data.

121
Imputation is conducted for all items; the resulting imputed data sets are reevaluated and
compared to the original data set and each other.
Multiple imputation is the most statistically robust method to account for data not missing
at random (Carpenter et al., 2006). Therefore, although there was a significant amount of data
missing in the participants’ responses, the missing data was managed via the most statistically
rigorous method. Although multiple imputation is a statistically robust method, imputed data is
extrapolated. It is modeled statistically to approximate participant responses as much as
possible; however, the statistical inferences may increase the likelihood of measurement error.
This is a limitation in the study because there is a possibility that the results using imputed data
could differ from how participants would respond if they completed the instrument in its entirety.
Implications
GGNPS revisions. The results of this study provide a number of insights that can be
used to guide further revisions of the GGNPS. Several items that were rated lowly by content
experts also performed poorly on the EFA. These items may be considered for revision or
removal.
Item P5_Q1 (“The DNA sequences of two randomly selected healthy individuals of the
same sex are 90-95% identical”) was a ‘True/False’ question, the correct response was ‘False.’
This item was the lowest rated item in the CVI (CVR = -.714). However, the low CVR may be
related to confusion among the experts. For example, one content expert indicated that the
percent similarity of DNA sequences is higher than 90-95%. The correct answer is ‘False’
because genetic similarity is closer to 99.5% (Levy et al., 2007). Five out of seven content
experts rated the item and ‘not relevant’ or ‘somewhat relevant,’ only two rated it as ‘relevant’ or
‘very relevant.’ However, this feedback should be cautiously considered, because other content
experts may have misread the question as well. Finally, this item did not load above .30 on any

122
factor in the EFA and did not demonstrate Thurstone’s (1947) simple structure. Despite the fact
that this item performed poorly on the EFA, recommendations to revise or remove this item
cannot be made without additional discussion with content experts due to possible
misinterpretation of the item.
Item P7_Q1_01 (“Do you intend to learn more about genetics?”) had one of the lowest
CVRs (.412). Three out of seven content experts rated the item and ‘not relevant’ or ‘somewhat
relevant,’ the remaining four rated it as ‘relevant’ or ‘very relevant.’ One content expert stated
the item may be misleading because all participants are likely to answer ‘yes.’ The item loaded
.308 on Factor 4 (competency/knowledge) and demonstrated Thurstone’s simple structure.
However, among the 7,798 responders, n = 2,540 replied ‘no’ and n = 2,751 replied ‘yes.’ The
remaining, n = 2,507, left the item blank. Therefore, participants were not more likely to answer
‘yes’ and did not seem to feel compelled to state they intend to learn more about genetics.
Question 2 in Part 7 of the instrument asked a follow up question about how helpful participants
found the following resources (e.g. books, web-based information, lectures, workshops) for
learning about genetics. However, this question was removed when the instrument was revised.
Furthermore, this question does not address accessibility. For example, a nurse may perceive
inperson workshops as very helpful, but only have time and financial resources available for
seeking out web-based information). Authors of the GGNPS may consider a follow up question
to provide insight into resources participants are most likely to use. This information can also be
used to create resources (e.g. webinars, in-person courses, clinical cases distributed via email
weekly, etc.) based on learner demand.
Table 19

123
Items with Low Factor Loadings and Associated CVRs
Item
Highest
Loading
Simple
Structure
CVR
P1_Q1
“How important is it for the nurse to become more
educated about the genetics of common diseases?”
.282
Absent
1
P1_Q3_04
“Potential disadvantages: would not improve patient
care.”
.292
Absent
N/A
P2_Q3_01
“A family history that includes only 1st degree relatives
such as… should be taken for every new patient.”
(shortened)
-.173
Absent
.714
P5_Q1
“The DNA sequences of two randomly selected healthy
individuals of the same sex are 90-95% identical.”
.118
Absent
-.714
P5_Q2
“Most common diseases such diabetes and heart
disease are caused by a single gene variant”
.132
Absent
1
P6_Q1
“Have you heard of the Essential Competencies… in
Genetics and Genomics?” (shortened)
.281
Absent
0.714
P7_Q1_02
“Would you be able to attend a course during work
hours?”
.116
Absent
1
P7_Q1_03
“Would you be able to attend a course on your own
time?”
.215
Absent
.714
A number of items did not load above .30 on any factor and did not demonstrate
Thurstone’s simple structure (see Table 19). However, most of those items, with the exception of
P5_Q1, were highly rated by the content experts. Additionally, the content experts did not
review item P1_Q3_04 because it was reworded when the GGNPS was initially revised. The
items that did not load above .30 on any factor may be considered for revision; however, these
results may also highlight a knowledge gap in particular content areas. An EFA evaluates shared
variance among data, if many of the participants answer an item incorrectly, with the same

124
incorrect answer, this decreases the covariance of this item with other items. As a result,
decreasing the ability of that item to load above .30 on any factor. Therefore, items must be
analyzed using the EFA results, the content expert analysis input, and evaluation of the topic
covered in the item.
For example, P2_Q3_01 (“A family history that includes only 1st degree relatives such as
parents, siblings, and children should be taken for every new patient”) addresses family history
collection, one of the most important components of evaluating genetic information. Not only
does this item address a key genetic/genomic concept, it also has a high CVR (.714). This item
may have loaded poorly (-.173) because participants did not know 1) how many generations are
included in a family history and/or 2) how frequently family history information should be
collected. The poor loading may be related to a knowledge deficit in one or both of the topics
addressed in the item. Additionally, it may be related to the question compounding two
concepts, if participants do not know the answer to either concept it could affect their response.
Item P5_Q2 (“Most common diseases such diabetes and heart disease are caused by a single
gene variant”) had a highest loading of .132. However, it had an extremely high CVR of 1. This
item should not be removed from the GGNPS because it addresses information that is directly
applicable to nursing practice. The low loading, but high CVR, may be related to a lack of
knowledge regarding the topic. The poor loading may also be related to the wording of the item;
participants may not understand the term ‘gene variant’ as opposed to ‘gene.’ Lastly, items
P7_Q1_02 (“Would you be able to attend a course during work hours?”) and P7_Q1_03
(“Would you be able to attend a course on your own time?”) did not load above .30 on any
factor and did not demonstrate Thurstone’s simple structure. However, they had high CVR
scores (see Table 19). While these items gather important background information about
availability and accessibility of education in genetics/genomics, these items are not clearly

125
associated with social systems, even though they are designated as social system items in the
GGNPS. For example, while attending a course during work could be related to the support a
health care setting (social system) provides, busy clinical units may not be able to accommodate
education during clinical time due to the demands of patient care. As a result, this item may not
accurately evaluate social system support. Similarly, attending a course outside of work may be
related to other time pressures such as family and/or personal responsibilities. Therefore, these
items provide very relevant information, but may be considered as part of
demographic/background information as opposed classifying them as a specific factor such as
social systems.
Items P7_Q1_02 and P7_Q1_03 parallel conflicts present in the clinical setting. Health
care institutions can provide social system support, such as continuing education for RNs.
Institutions have educational departments, direct access to nursing staff, and conduct ongoing
evaluation of patient care needs. However, health care institutions are also often the source of
barriers to gaining knowledge about genetics/genomics, negative attitudes, and decreased
adoption. These barriers are frequently related to time pressures such as poor staffing ratios and
work-related stressors. The GGNPS aims to comprehensively evaluate how genetics/genomics
are integrated into the clinical setting, including exploring knowledge/competency, confidence,
attitudes/receptivity, decision/adoption, as well as the role of social systems. However, each of
these components are individually complex. Particularly complex components, especially ones
where the relationship to other variables is not clear, such as social systems, should be further
evaluated in more focused analyses. Analyses may include focus groups to gain specific insight
into the relationship between health care institutions, nursing staff, facilitators/barriers to
continuing education, and which components encompass the variable of social systems. Such
focused analyses can further inform next steps and further analyses of the GGNPS.

126
Future analyses of construct validity. The EFA results shed light on why the CFA
analysis was unable to produce loadings. Some items designated as one variable in the GGNPS,
actually loaded on a different variable; as a result, the CFA was unable to identify factor loadings
based on the current GGNPS item designations.
Furthermore, some items in each variable (with the exception of confidence) actually
loaded on another variable, potentially resulting in measurement error. This measurement error is
compounded when evaluating direct and indirect relations among five variables. This provides
insight into many of the weak relations in the SEM; if the variables were measured incorrectly, as
indicated by the EFA, relations between the variables cannot be accurately evaluated. The SEM
should be reevaluated following revision of the variables.
In the SEM analysis of the original instrument, used by family physicians, Jenkins and
colleagues (2010) also noted that adoption of genetics/genomics did not follow the path predicted
by Rogers. Instead, there were two paths leading to adoption of genomic-related innovations:
one path based on ‘comfort’ with using genetics/genomics in clinical practice and a second path,
based on ‘relevance’ to clinical practice. The researchers hypothesized that the multiple paths
may be related to the complexity of the innovation, genetics/genomics, and complexity of clinical
practice itself. They contrasted this to the linear nature of Rogers’ DOI model. In clinical
practice, providers are influenced by a variety of factors, including the condition affecting the
patient and the provider’s approach to clinical practice. In the current study, the SEM results
demonstrated a lack of fit between the hypothesized model, based on Rogers’ DOI model, and
the data. Alternative paths will be explored in future analyses. However, prior to this, the EFA
results will be used to reclassify the variables, because many items did not load as predicted.
After reclassifying the variables, the SEM will be reevaluated. Alternative paths will be

127
considered by exploring both additional components of Rogers’ DOI model and paths related to
clinical practice, as reported by Jenkins and colleagues.
Future studies can also explore the effect of additional components of Rogers’ (2003)
DOI theory on adoption of genetics/genomics into nursing practice. For example, characteristics
of decision-making units and prior conditions. Although these components of Rogers’ theory are
not evaluated in the GGNPS, they can be studied using qualitative analyses to gain a focused
understanding of this portion of the theory. Specifically, innovativeness may be reflected by
adoption of other innovations, for example technologies such as electronic medicals records
(EMRs) and the adoption of innovations in one’s personal life. This would provide insight into
adoption of an innovation that is mandated by a nurse’s employer (e.g. EMR), as well as how
participants explore innovations on their own time. Felt needs/problems can be explored based
on nurses’ reports of what they need to effectively provide patient care and potential barriers in
the workplace. The researcher would attempt to identify themes related to how these
components of Rogers’ DOI theory affect adoption of genetics/genomics into nursing practice.
Evaluation of perceived characteristics of an innovation can provide additional insight
into barriers and facilitators of adopting genetics/genomics. These characteristics include relative
advantage, compatibility, complexity, trialability, and observability. The relative advantages of
using genetics/genomics are significant, for example allowing nurses to use the most up-to-date
clinical resources to guide screening, diagnosis, treatment selection, and health promotion. In
addition, because essentially all diseases have a genetic/genomic component, nurses are strongly
advantaged by having an understanding of this content and being able to use it in their clinical
practice (“FAQ About Genetic Disorders,” 2012). However, poor knowledge of
genetics/genomics may result in nurses not being aware of these advantages.

128
In addition, genetics/genomics may be incompatible with clinical institutions that do not
champion continued education about the topic, those that do not value the role of family history
evaluation, patient education about the genetic basis of disease, and/or identifying patients who
may benefit from referrals to genetic specialists. If the social system of the institution does not
emphasize and champion the role of genetics/genomics, it makes it increasingly difficult for
nurses to adopt it into their clinical practice. As a result, nurses will receive mixed messages
about patient care priorities. On one hand, nurses must administer medications and respond to
call bells in a timely manner, document carefully, and strive for high patient satisfaction, despite
poor nurse-to-patient ratios. On the other hand, institutions maintain that nurses must be current
in their clinical practice, although they may not provide the resources to help nurses learn about
and adopt clinical innovations. The resulting incompatibility may affect not only the feasibility
of adopting innovations, but also nurses’ attitudes/receptivity towards those innovations, as well
as their ability to increase their knowledge/competency and confidence toward the innovation.
Similarly, many aspects of genetics/genomics are complex; this complexity is a barrier to
the adoption of this content into nursing practice. The body of knowledge of genetics/genomics
is vast, information is frequently updated, and some concepts are intimidating for individuals
with no previous genetic/genomic experience. Also, adoption of genetics/genomics requires
clinical knowledge, associated skills (such as family history collection), and actions (such as
patient advocacy, patient education, and facilitating referrals).
Unlike some innovations that users can trial and evaluate prior to full adoption,
genetics/genomics have low trialability. Potential adopters cannot ‘try’ genetics/genomics like a
new computer and decide to adopt or reject it. This complexity, coupled with possible
incompatibility at some institutions, and the lack of ease of ‘trying’ the innovation before
adoption, makes genetics/genomics more difficult to adopt.

129
Not only are genetics/genomics more difficult to adopt, because it is an innovation that
affects so many aspects of patient care and has so many components, it is also difficult to observe
the adoption of this innovation. For example, nurses on a unit may see their colleagues using a
new piece of technology; they can easily observe this new technology/equipment in use and it
may promote the spread of an innovation in that social system. However, adoption of
genetics/genomics is not as easily observable. That affects the spread of the innovation among
their peers, other nurses may not recognize that their colleagues are using the innovation, and are
less likely to consider it for adoption to their practice. Decreased observability also makes
measuring adoption of genetics/genomics more difficult.
To overcome the difficulty of measuring adoption of genetics/genomics, it is important to
define how adoption is measured. Essential Competencies and Curricula Guidelines for Nurses
in Genetics and Genomics (2009) identify nursing roles and responsibilities required to adopt
genetics/genomics. These include collection and evaluation of family history information,
patient education, facilitating genetic referrals if warranted, and using genetic/genomic
information in clinical decision-making. All of these roles and responsibilities are reflected in
the GGNPS. Accurately evaluating adoption is essential because genetics/genomics affect how
we screen for, diagnose, and manage disease. In addition, genetics/genomics play a role in health
promotion and maintenance. Therefore, establishing validity of the GGNPS is essential to
measure adoption of genetics/genomics, assess a potential lack of adoption, and develop
strategies to promote the use of genetics and genomics in nursing practice to provide current,
safe, and effective patient care.
Implications for Nursing Research and Education
The GGNPS has a variety of applications for nursing education, practice, and research.
In nursing education, the GGNPS can be used to identify gaps in knowledge and create targeted

130
educational interventions. For example, it can be used to create continuing education initiatives
among practicing nurses and evaluate how those initiatives affect adoption of genetics/genomics
into nursing practice.
As the body of genetic/genomic knowledge rapidly expands, nursing curricula must also
incorporate this new information. Nursing programs increasingly focus on knowledge synthesis
and application to graduate nurses who can think critically and provide safe, competent patient
care. The GGNPS reflects needs of academic programs by evaluating both genetic/genomic
knowledge and applications of that content into nursing practice.
Genetics/genomics are pervasive in nursing practice, regardless of role or specialty.
Therefore, this content should be evaluated on licensing exams; however, integration of
genetics/genomics into licensing exams is a complex and ongoing process. New content is added
to licensing exams, such as the NCLEX, via multiple routes. Publications from the National
Council of State Boards of Nursing (NCSBN) (2016) state that the exam is updated with
evidence derived from clinical outcomes and by surveying newly licensed RNs in the first six
months of practice. Newly licensed RNs describe a list of activities based on their clinical
practice and this information is referenced for updating the NCLEX exam. However, because
integration of genetic/genomic content into nursing curricula is lagging, new graduates may not
be aware of their professional roles and responsibilities in relation to genetics/genomics or how
to use genetics/genomics in nursing practice. Similarly, new RNs are often task-based and
prioritize responsibilities such as medication administration and charting (Feng & Tsai, 2012).
As a result, because newly licensed RNs are less likely to consider the comprehensive roles and
responsibilities of a nurse, including genetic/genomic competencies, this content is less likely to
be integrated into NCLEX. Furthermore, a lack of questions on the licensing exam further
undermines the need to integrate genetics/genomics into nursing curricula. In addition, the lag in

131
integrating genetics/genomics into nursing curricula decreases its use in clinical practice; as a
result, less is known about how clinical outcomes are affected by genetics/genomics, which also
decreases its integration into content on licensing exams.
Evaluation of the NCLEX Detailed Test Plan (2016) references family history of
testicular cancer as a risk factor for increased risk of developing testicular cancer. Although that
information is correct, it is a very low level application of genetic/genomic knowledge. The
second reference to genetics/genomics is that performing a health history should include a
“genetic history” (National Council of State Boards of Nursing, 2016, p. 20). This is mentioned
in relation to health screening with no discussion of how to collect family history information for
multiple generations or use is it clinical decision-making. The current genetics/genomics content
in the NCLEX Test Plan is sparse and does not reflect the myriad of ways genetics/genomics
affects nursing practice and patient outcomes. The GGNPS can be incorporated into licensing
exam content to evaluate how genetic variation can affect disease processes and nurses' roles in
providing referrals, patient education, and advocacy.
Adoption of genetics/genomics into nursing practice is a complex process, affected by
many variables. In clinical practice, the GGNPS can be used to evaluate variables that are
facilitators and barriers to adoption of genetics/genomics. Evaluation of not only adoption, but
associated variables, is important because evidence indicates not only are genetics/genomics not
being fully adopted into clinical nursing practice, but inadequate knowledge, poor understanding
about relevance, inadequate confidence, and inconsistent support from social systems all
contribute to a lack of adoption (Calzone, Jenkins, Culp, Caskey, & Badzek, 2014; Calzone,
Jenkins, Culp, Bonham, & Badzek, 2013; Kirk, Lea, & Skirton, 2008).
A number of structural factors contribute to these barriers. For example, Calzone and
colleagues (2014) reported that following licensure, 86.8% (n = 4,594/5,294) of RNs

132
participating in a study did not complete any courses focusing on genetics/genomics. A lack of
learning opportunities directly contributes to inadequate knowledge about the topic. Social
system pressures are demonstrated by Sussner and colleagues (2011), inadequate time and a high
workload were reported as major barriers to collection of family history information. This can
also adversely affect nurses’ attitudes/receptivity; inadequate time and many additional
responsibilities may make nurses less likely to adopt genetics/genomics.
Additional structural barriers include a lack of a designated location to document family
history information and the inability to reference family history information that may have been
documented in the electronic health record (EHR) (Kho et al., 2011). As a result, nurses are
unsure of where to initially document the information or how to find family history information
that is located in an EHR. Barriers to adoption of genetics/genomics in clinical practice must be
addressed because genetics/genomics play an important role in both disease prevention and
health promotion. In managing clinical conditions, genetics/genomics affect screening,
diagnosis, treatment selection, and patient-education. Therefore, genetics/genomics are within the
scope of practice of all nurses, regardless of academic preparation, specialty, or clinical roles
(Jenkins & Calzone, 2007)
A lack of integration of genetics and genomics into nursing education and practice can be
addressed by championing nursing research. For example, future studies will use findings from
the EFA and feedback from content experts to restructure variables in the GGNPS and reevaluate
construct validity using both SEM and CFA analyses. Upon establishing face, content, and
construct validity, the GGNPS can be used to identify barriers to adoption of genetics/genomics,
develop initiatives to promote adoption, and use data from these initiatives to increases nurses’
knowledge, improve confidence, promote positive attitudes/receptivity, and increase social
system support. Additional focused, in-depth analyses can concentrate on complex factors such

133
as social systems. Analyses can focus on how health care institutions support the use of
genetics/genomics in nursing practice with evaluation of clinical sites who are early and effective
adopters. Additional focused studies can consider how decision-making units (e.g. peernetworks
in employment settings) affect nurses’ attitudes. Such focused initiatives can further inform
evaluation of the GGNPS. With continued evaluation of validity, the GGNPS can be used for a
variety of applications in nursing research, education, and clinical practice.
Appendix A
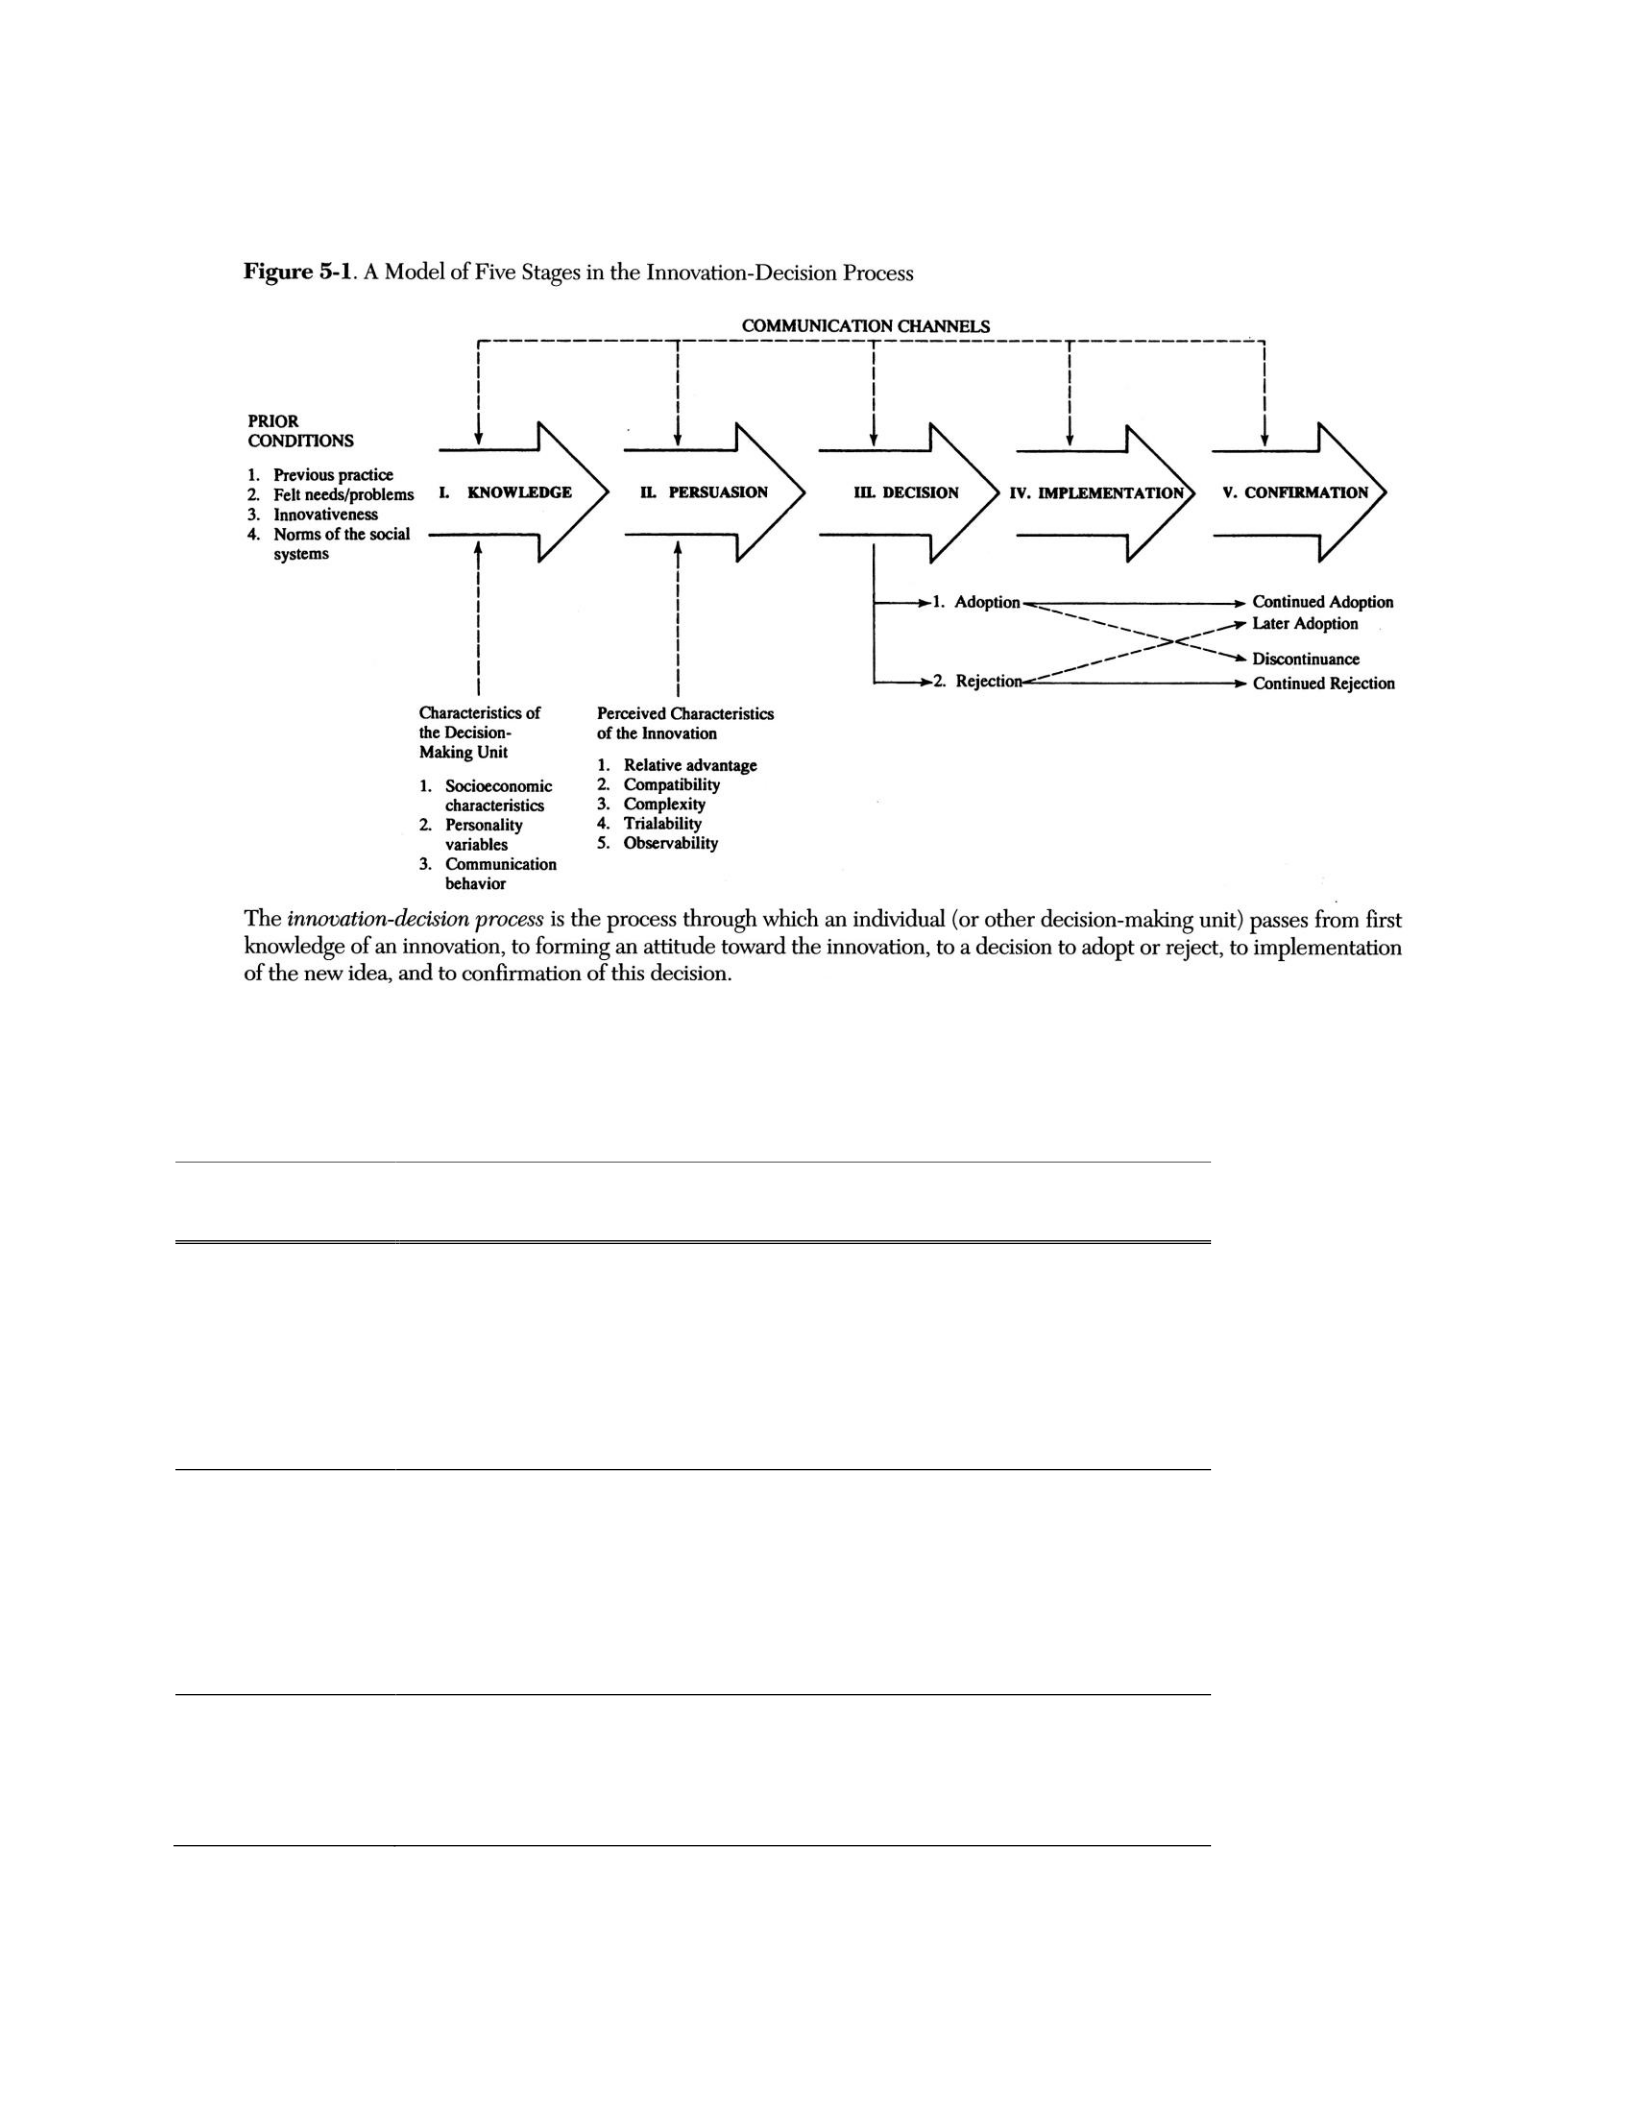
134
Diffusion of Innovations (DOI) Model
Appendix B
Knowledge Score Components
Item
Content
P2_Q3_01
“A family history that includes only 1st degree relatives such as
parents, siblings, and children should be taken for every new
patient.”
P2_Q3_02
“A family history that includes 2nd and 3rd degree relatives
such as grandparents, aunts, uncles, and cousins should be
taken for every new patient.”
P2_Q3_03
“Family history taking should be a key component of nursing
care.”

135
P2_Q3_04
“There is a role for nurses in counseling patients about
genetic risks.”
P4_Q1_01
“Do you think genetic risk has clinical relevance for: Breast
cancer.”
P4_Q1_02
“Do you think genetic risk has clinical relevance for: Colon
cancer.”
P4_Q1_03
“Do you think genetic risk has clinical relevance for:
Coronary heart disease.”
P4_Q1_04
“Do you think genetic risk has clinical relevance for:
Diabetes.”
Added after
revision
Extent to which family history supports clinical decisions
(such as administering drugs prescribed).
P5_Q1
“The DNA sequences of two randomly selected healthy
individuals of the same sex are 90-95% identical.”
P5_Q2
“Most common diseases such as diabetes and heart disease are
caused by a single gene variant.”
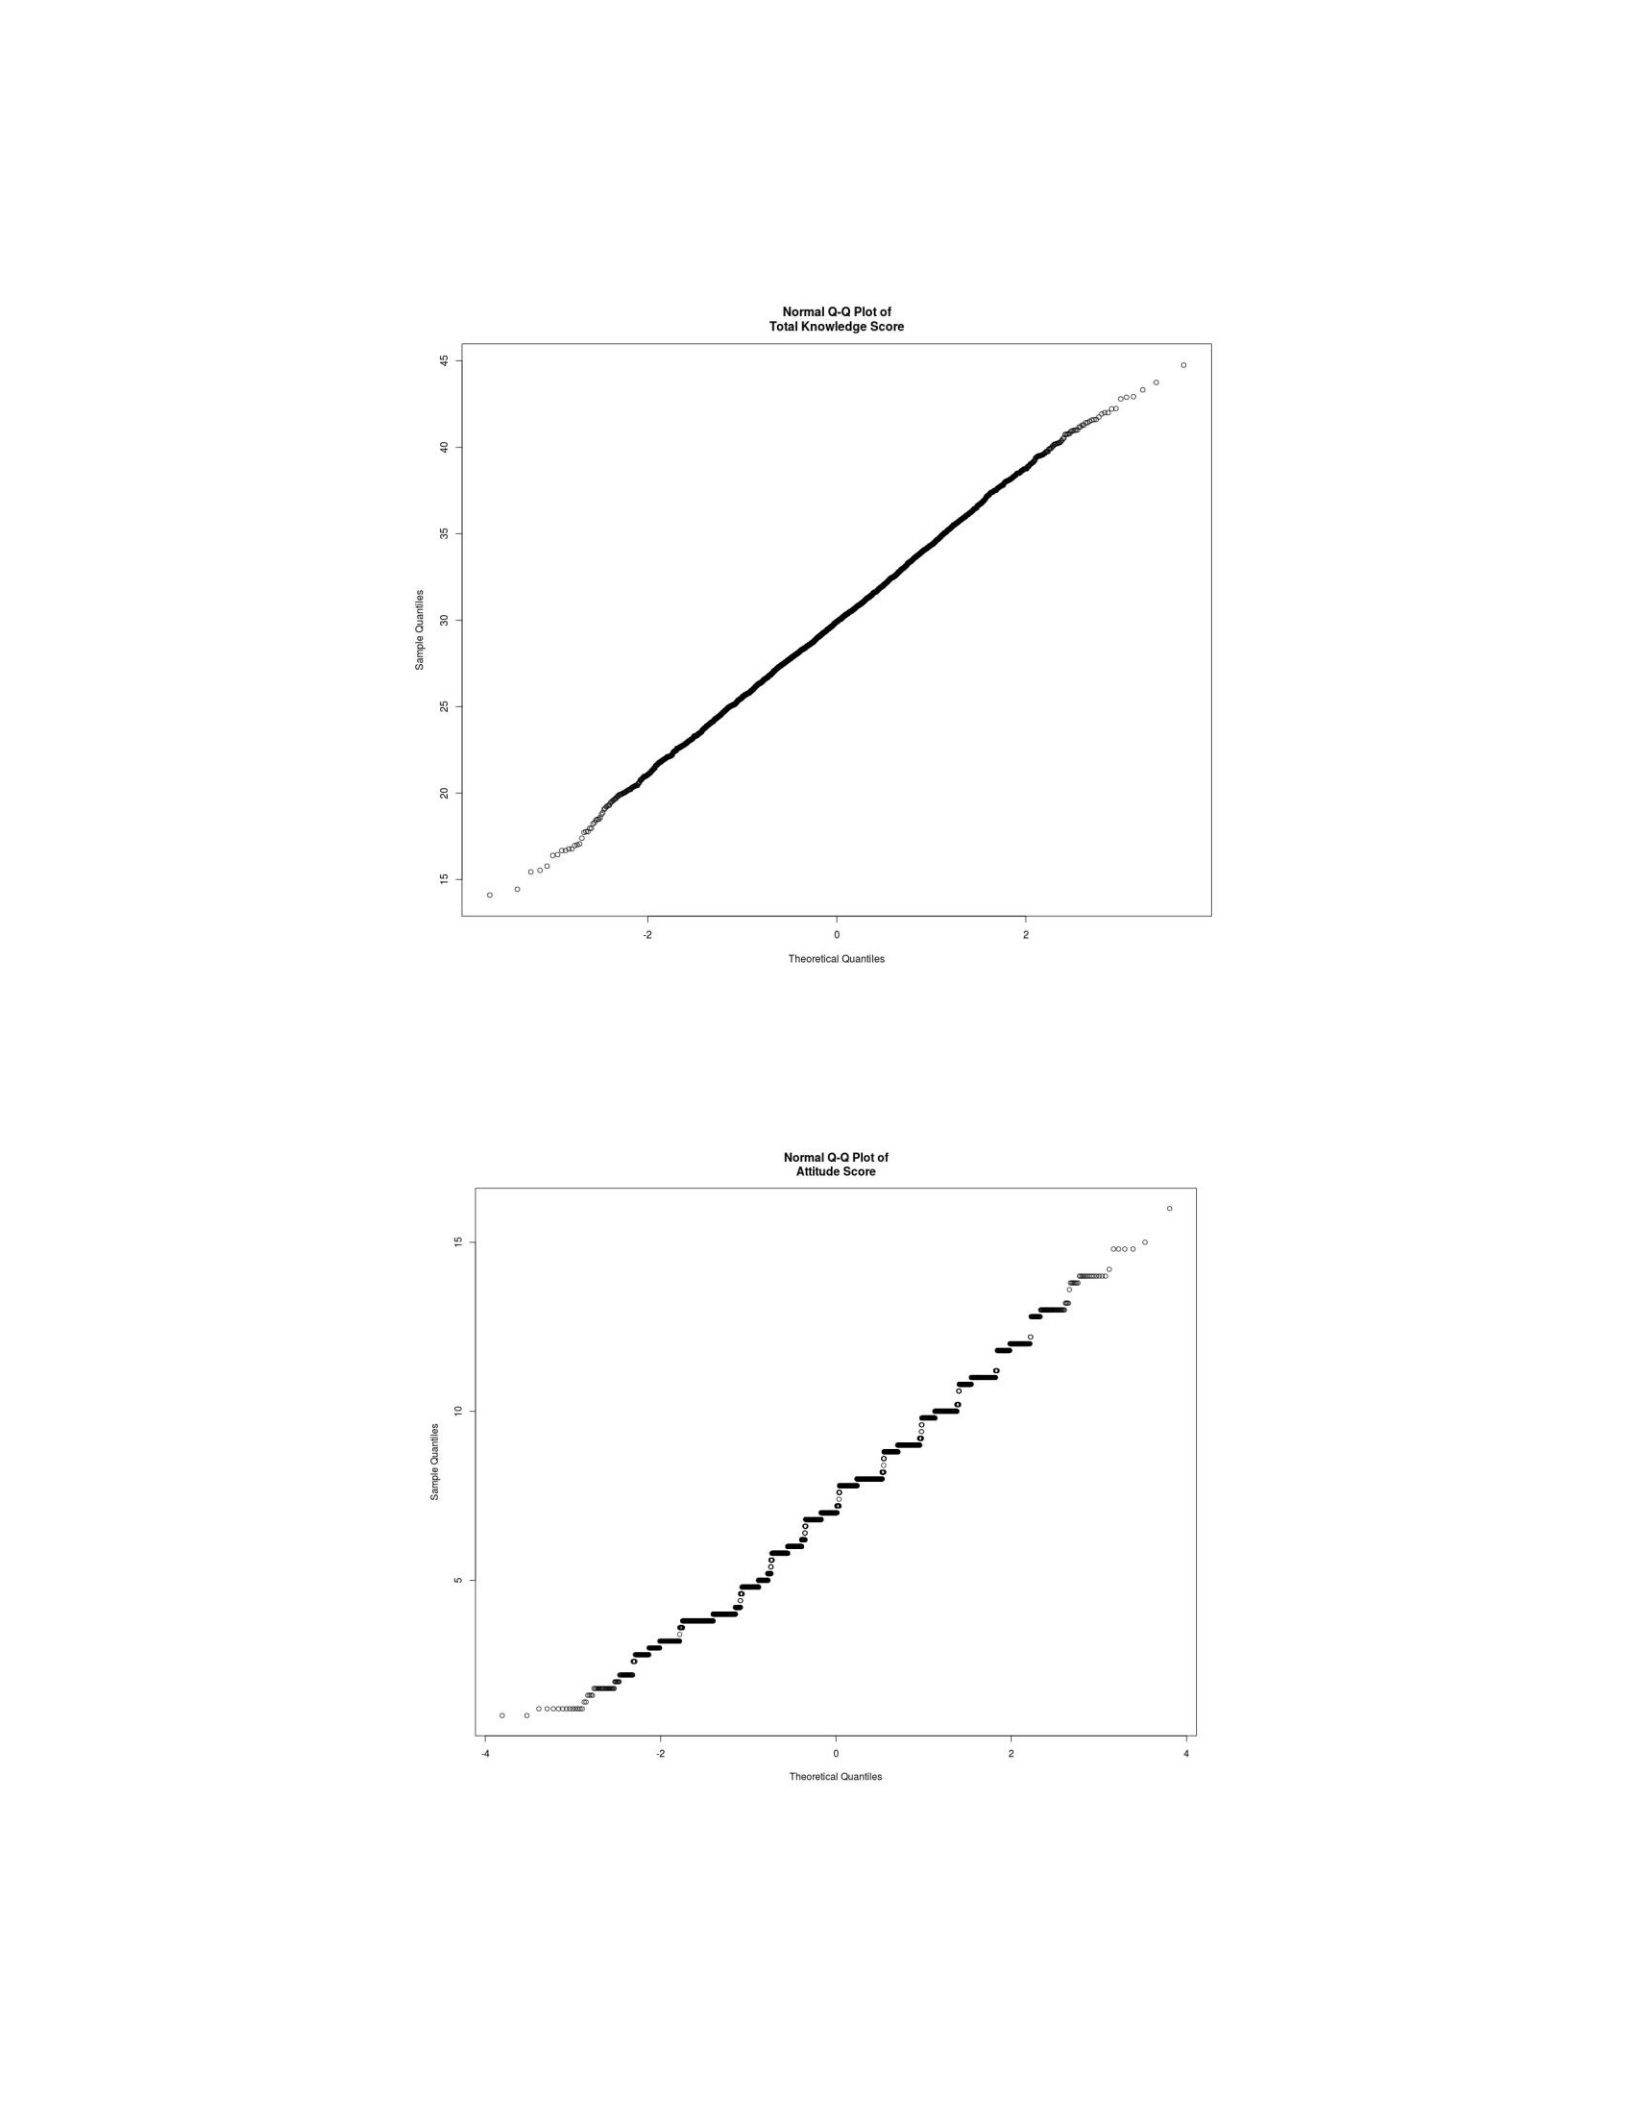
136
Appendix C.1
Q-Q Plot of Items Comprising the “Knowledge” Variable
Appendix C.2
Q-Q Plot of Items Comprising the “Attitude” Variable
Appendix C.3.
Q-Q Plot of Items Comprising the “Confidence” Variable
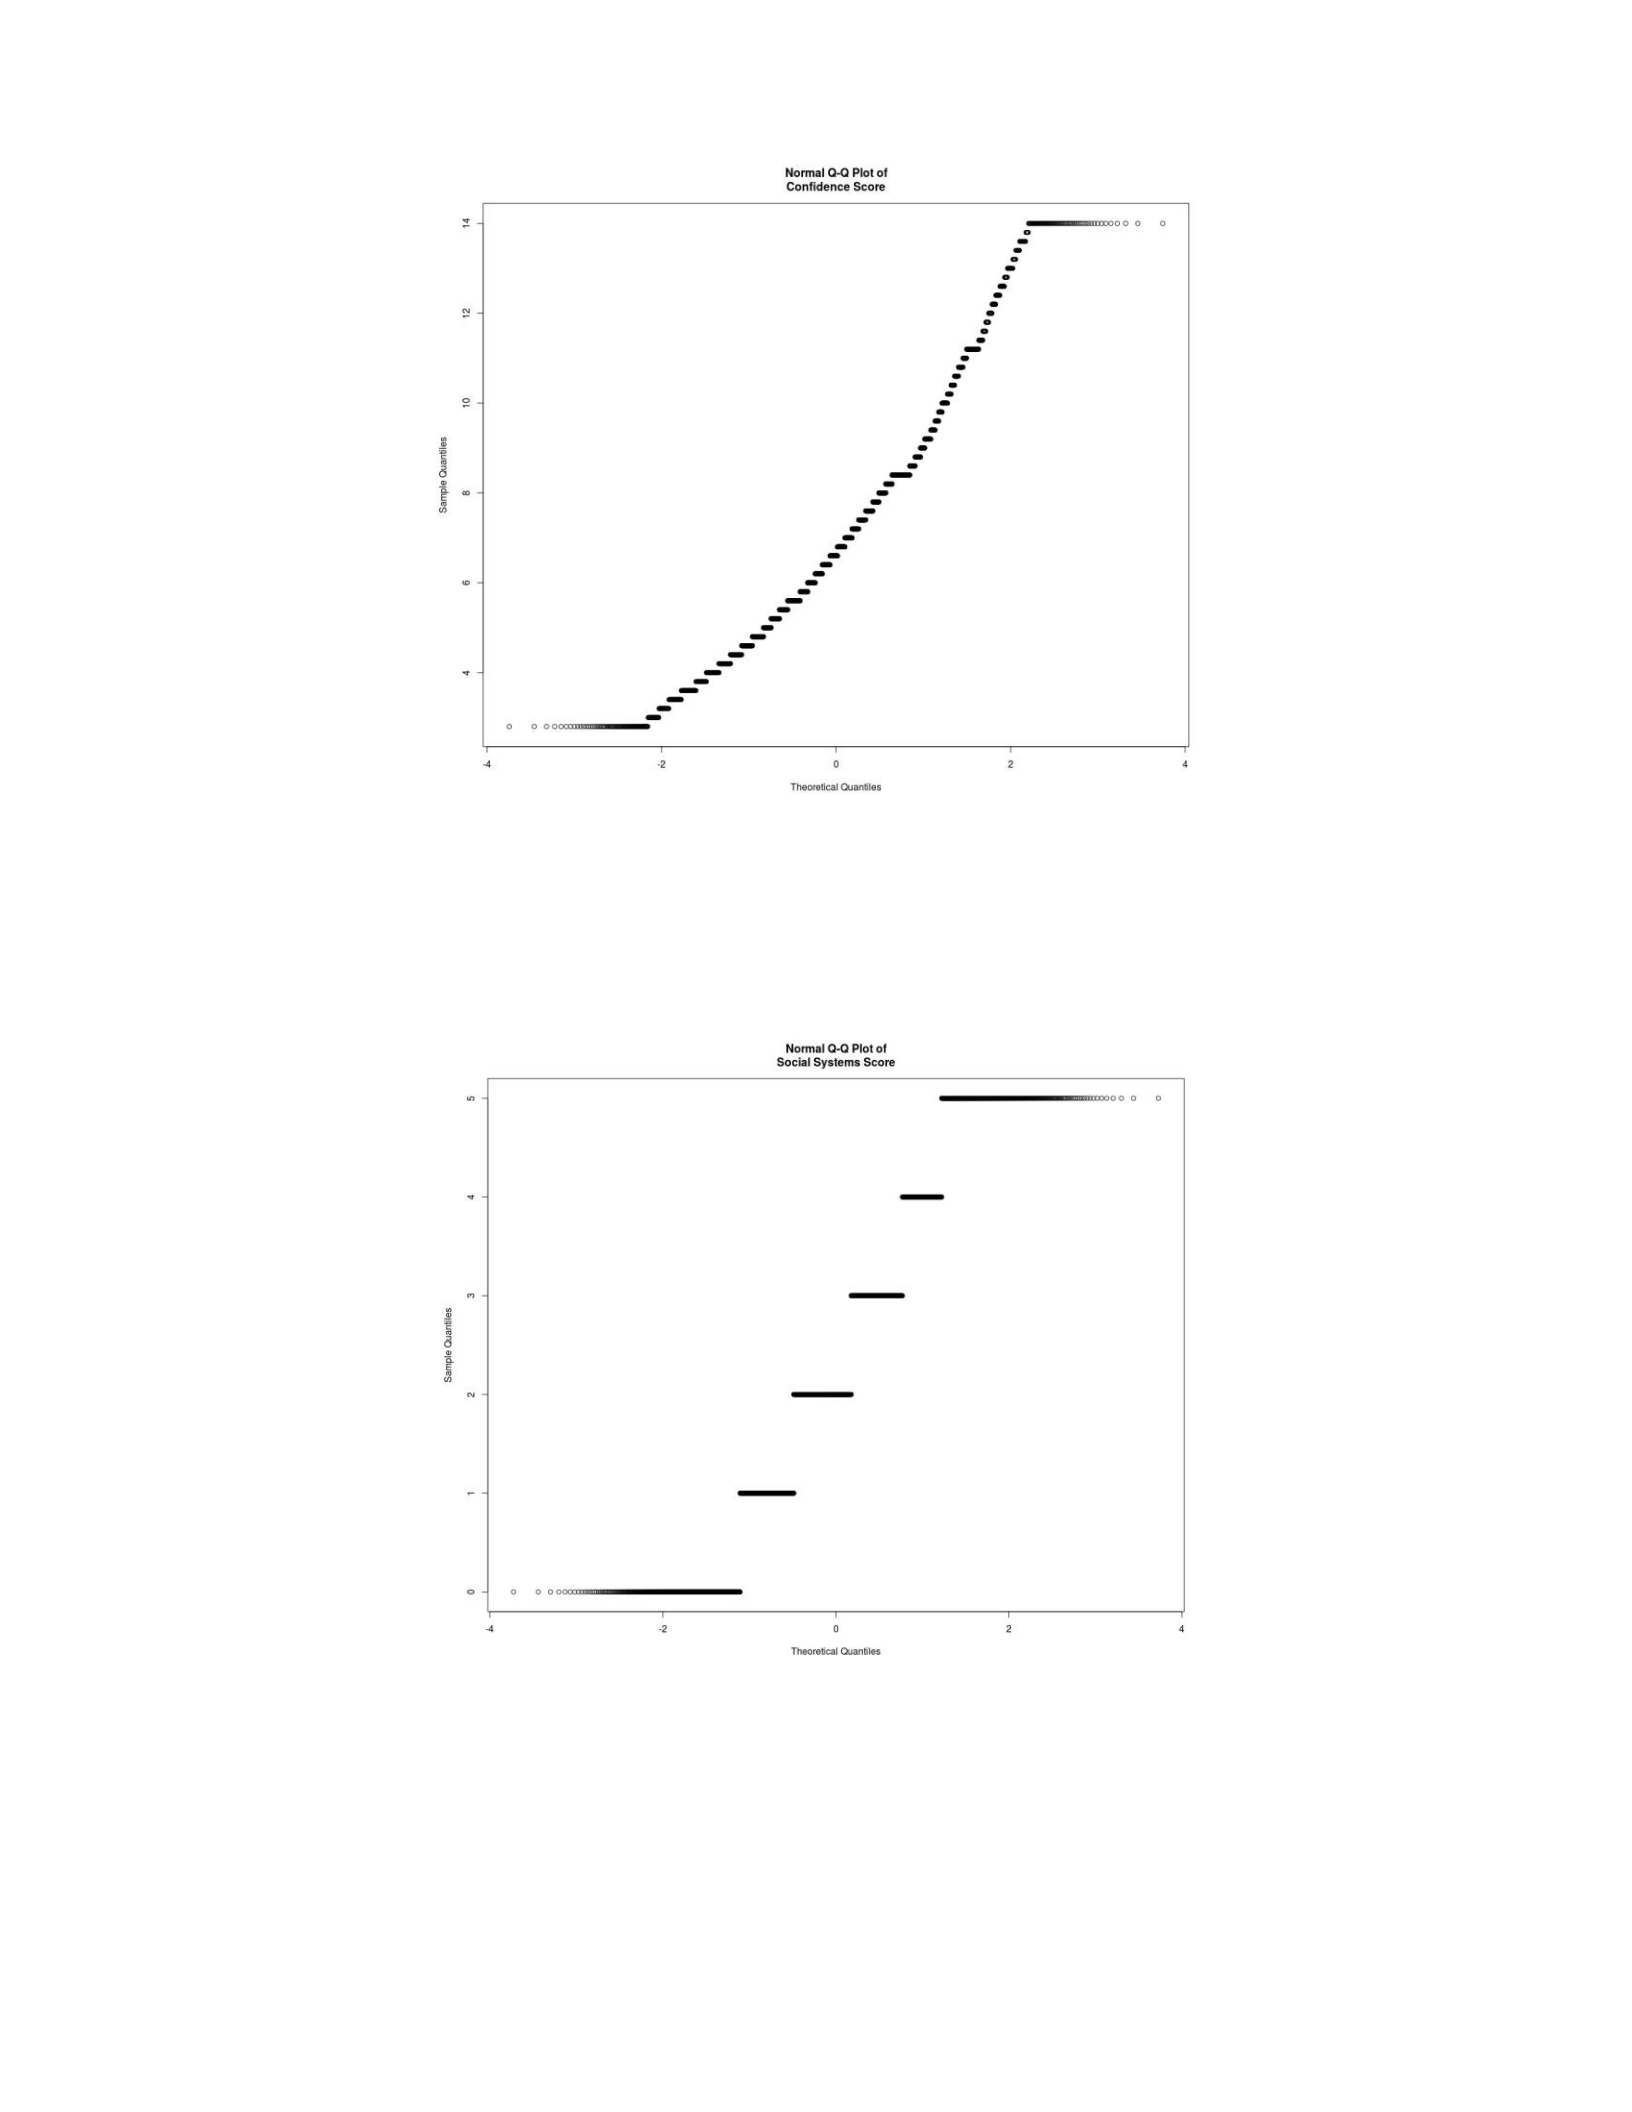
137
Appendix C.4.
Q-Q Plot of Items Comprising the “Social Systems” Variable
Appendix C.5.
Q-Q Plot of Items Comprising the “Adoption” Variable
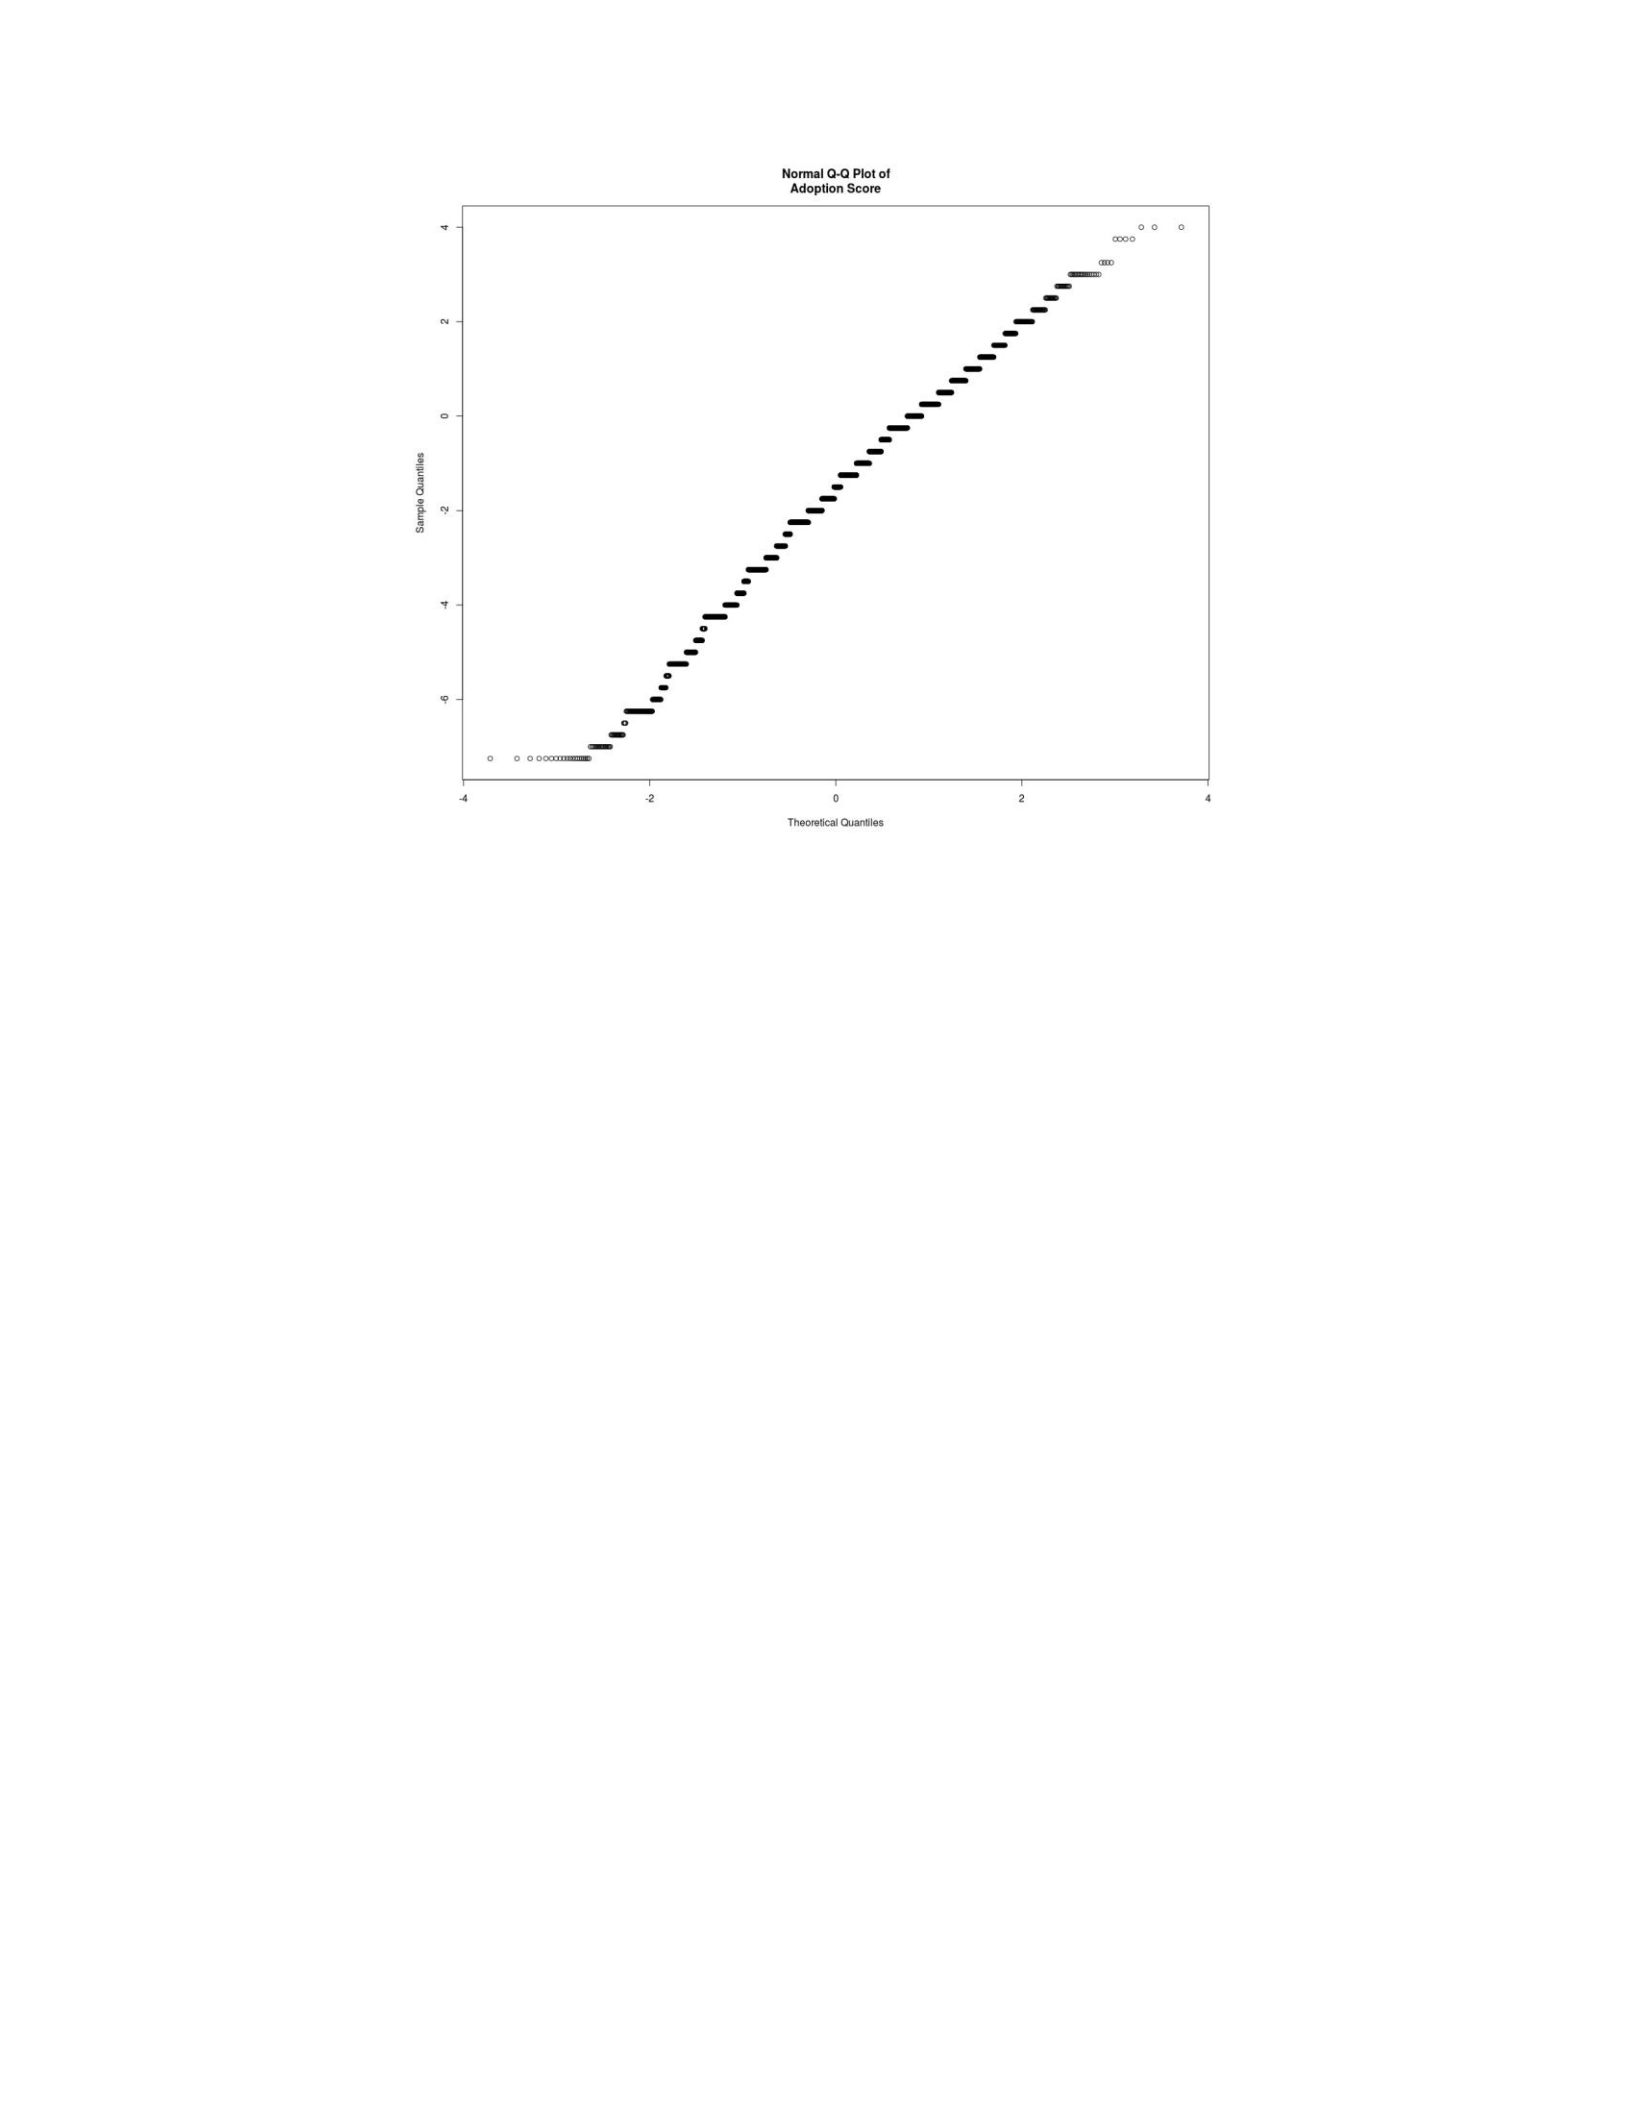
138

139
Appendix D.
Welch-Two Sample T-Tests
Part 3, Question 4, Section 1 p
= 0.891
Confidence → Attitudes/Receptivity
.05
Part 1, Question 1 p
= 0.9769
Social Systems → Competency/knowledge .00205 Part 2, Question
3, Section 1 p = 0.7388
Part 2, Question 3, Section 2
p = 0.809
Part 2, Question 3, Section 3
p = 0.6151
Part 2, Question 3, Section 4
p = 0.8481
Part 4, Question 1, Section 1
p = 0.6694
Part 4, Question 1, Section 2
p = 0.7097
Part 4, Question 1, Section 3
p = 0.7077
Part 4, Question 1, Section 4
p = 0.7691
Part 4, Question 1, Section 5
p = 0.5768
Part 4, Question 1, Section 6
p = 0.9776
Variables
Family
-
wise
Alpha value
p
value
Confidence
→
Decision/Adoption
.0127
Part 3, Question 2
p
=
0.268
Part 3, Question 3
p
=
0.338
Part 3, Question 4, Section 1
p
=
0.593

140
Part 4, Question 2, Section 1
p = 0.3955
Part 4, Question 2, Section 2
p = 0.5243
Part 4, Question 2, Section 3
p = 0.321
Part 4, Question 2, Section 4
p = 0.529
Part 4, Question 2, Section 5

141
p = 0.6829
Part 4, Question 4, Section 1
p = 0.4489
Part 4, Question 4, Section 2
p = 0.4771
Part 4, Question 4, Section 3
p = 0.07002
Part 4, Question 4, Section 4
p = 0.1501
Part 4, Question 4, Section 5
p = 0.449
Part 4, Question 4, Section 6
p = 0.5425
Part 5, Question 1
p = 0.9821
Part 5, Question 2
p = 0.9327
Part 6, Question 1
p = 0.7105

142
Part 3, Question 3 p

143
Part 6, Question 2, Section 1
p = 0.8404
p = 0.02784 Part 3, Question 3
p = 0.02431
Part 3, Question 4, Section 1
p = 0.02998
Part 3, Question 4, Section 2 p
= 0.008711
Social Systems → Attitudes/Receptivity
.05
Part 1, Question 1 p
= 0.7577
Attitudes/Receptivity → .127 Part 3, Question 2
Decision/Adoption p < 0.001
Part 3, Question 3
p < 0.001
Part 3, Question 4, Section 1
p < 0.001
p < 0.001
Competency/knowledge → .127 Part 3, Question 2
Decision/Adoption p < 0.001
Part 3, Question 4, Part 1 p
< 0.001
Part 2 Question 1, Section 2
p = 0.9102
Part 2, Question 1, Section 3
p = 0.9806
< 0.001
Part 6, Question 2, Section 2
p
=0.7472
Social Systems
→
Decision/Adoption
.127
Part 3, Question 2
Part 3, Question 4, Section 2
Part 3, Question 4, Part 2
p
<
0.001
C
ompetency/knowledge
→
Confidence
.0366
Part 2 Question 1, Section 1
p
=
0.999

144
Part 2, Question 1, Section 4
p = 0.6327
Part 2, Question 1, Section 5
p = 0.5057
Part 2, Question 1, Section 6
p = 0.4773
Part 2, Question 1, Section 7
p = 0.8218
Part 2, Question 1, Section 8
p = 0.5948
Part 2, Question 1, Section 9
p = 0.7042
Part 2, Question 1, Section
10 p = 0.8568
Part 2, Question 1, Section
11 p = 0.8496
Part 2, Question 1, Section
12 p = 0.7663
Part 2, Question 1, Section
13 p = 0.6453
Part 7, Question 1, Section 2
p < 0.001
Part 7, Question 1, Section 3
p < 0.001
Part 7, Question 1, Section 4
p < 0.001
Part 2, Question 1, Section 14
p
=
0.753
Decision/Adoption
→
Social Systems
.102
Part 7, Question 1, Section 1
p
<
0.001

145
Part 7, Question 1, Section 5 p
< 0.001
Decision/Adoption → Attitudes/Receptivity
.0032
Part 1, Question 1 p
< 0.001
Decision/Adoption →
.00366
Part 2, Question 1, Section 1
Competency/knowledge p < 0.001
Part 2, Question 1, Section 2
p < 0.001
Part 2, Question 1, Section 3
p < 0.001
Part 2, Question 1, Section 4
p < 0.001
Part 2, Question 1, Section 5
p < 0.001
Part 2, Question 1, Section 6
p < 0.001
Part 2, Question 1, Section 7
p < 0.001
Part 2, Question 1, Section 8
p < 0.001
Part 2, Question 1, Section 9
p < 0.001
Part 2, Question 1, Section
10 p < 0.001
Part 2, Question 1, Section
11 p < 0.001
Part 2, Question 1, Section
12 p < 0.001
Part 2, Question 1, Section
13 p < 0.001

146
Part 2, Question 1, Section 14
p
<
0.001
147
Appendix E
Content Validity Index and Ratio
Domain: Attitudes/Receptivity
Conceptual definition: “The relative advantage offered by the innovation. Perceived attributes of the
innovation including the recognized need for the innovation, as well as contextual factors such as
identification of communication channels that facilitate or hamper adoption and sustained
implementation” (Calzone et al., 2012, p. 12).
Contextual definition: “Perceived importance, advantages, and disadvantages of integrating genomics
into practice. The complexity of integrating family history into practice. Perception of the value of
family history in patient care and their personal practice” (Calzone et al., 2012, p. 12).
1. Please indicate whether you think each of the following
would be a potential disadvantage of integrating genetics of
common diseases into your practice:
Relevancy (1-4)
1- Not
relevant
2- Somewhat
relevant
3- Relevant
4- Very
relevant
1
2
3
4
CVR
1
*
6
0.714
5
2
1
1
1
5
0.714
1
2
4
0.714
1
3
3
0.714
148
* Frequency of responses
Domain: Attitudes/Receptivity cont.
2. Please indicate whether you think each of the following
would be a potential advantage of integrating genetics of
common diseases into your practice:
3. How important do you think it is for the nurse to become
more educated about the genetics of common diseases?
Very important Somewhat important Not very
important Not at all important Neutral
Don’t know
Relevancy (1-4)
1- Not
relevant
2- Somewhat
relevant
3- Relevant
4- Very
relevant
1
2
3
4
CVR
1
6
1
1
1
5
0.714
1
1
5
0.714
Relevancy (1-4)
1- Not
relevant
2- Somewhat
relevant
3- Relevant
4- Very
relevant
1
2
3
4
CVR
1
6
1
No Advantage
Advantage
Better treatment
decisions (e.g., which
drugs to prescribe)
Improved services to
the patients
Better adherence to
clinical
recommendations
among patients
149
4. Please indicate whether you agree or disagree with the
following statements.
Domain: Confidence
Conceptual definition: “Level of certainty that knowledge about the innovation is accurate” (Calzone et
al., 2012, p. 12).
Contextual definition: “Confidence in: discussing genetics with patients; deciding what family history
information is relevant to assessing genetic susceptibility; availability, risks, benefits and limitations of
genetic testing; facilitating referral for genetic services” (Calzone et al., 2012, p. 12).
Relevancy (1-4)
1- Not
relevant
2- Somewhat
relevant
3- Relevant
4- Very
relevant
1
2
3
4
CVR
1
6
1
Relevancy (1-4)
1- Not
relevant
2- Somewhat
relevant
3- Relevant
4- Very
relevant
1
2
3
4
CVR
2
5
1
1
6
1
1
6
1
Agree
Disagree
Don't Know
Family
history taking
should be a
key
component of
nursing care.
150
5. Each of the following statements relates to the genetics of
common diseases and family history taking. By common
diseases, we are referring to disorders that arise as a result
of interactions between an individual’s environment and
his or her unique genetic makeup. Common diseases include
diseases such as cancer, heart disease, and diabetes. Please
indicate how confident you are that you can do each of
the following:
Decide what family history information is needed to tell
something about a patient’s genetic susceptibility to
common diseases.
Discuss how family history affects recommended screening
intervals.
Decide which patients would benefit from a referral for
genetic counseling and possible testing for susceptibility to
common diseases
Access reliable and current information about genetics and
common diseases.
Give patients information about the risks of genetic testing
for common diseases
Give patients information about the benefits of genetic
testing for common diseases.
Give patients information about the limitations of genetic
testing for common diseases.
Facilitate referrals for genetic services for common
diseases.
Not at all Confident confident
Domain: Competency/ Knowledge
Conceptual definition: “Recognition of the innovation and evidence of understanding the innovation and
its function” (Calzone et al., 2012, p. 12).
Contextual definition: “Knowledge of the genomics of common disease, and the family history
information needed to evaluate patients’ genetic susceptibility” (Calzone et al., 2012, p. 12).
1
6
1
1
3
3
0.714
1
3
3
0.714
2
2
3
0.429
1
2
4
0.714
151
6. Please indicate whether you agree or disagree with the
following statements.
Relevancy (1-4)
1- Not relevant
2- Somewhat relevant
3- Relevant
4- Very relevant
1
2
3
4
CVR
1
1
5
0.714
2
5
1
2
5
1
152
7. Do you think that genetic risk (e.g., as indicated by family
history) has clinical relevance for the following:
Domain: Competency/ Knowledge cont.
8. When patients indicate a disorder in the family, which of
the following pieces of information do you collect in your
standard family history assessment? Each family member’s:
** One reviewer left answer blank
9. Thinking about how you support clinical decisions (such as
administering drugs prescribed), how important do you think
each of the following is to consider?
Relevancy (1-4)
1- Not relevant
2- Somewhat relevant
3- Relevant
4- Very relevant
1
2
3
4
CVR
7
1
7
1
1
6
1
1
6
1
7
1
Relevancy (1-4)
1- Not relevant
2- Somewhat relevant
3- Relevant
4- Very relevant
1
2
3
4
CVR
1
6
1
1
6
1
1
1
5
0.714
1
6
1
6**
0.714
Relevancy (1-4)
1- Not relevant
2- Somewhat relevant
3- Relevant
4- Very relevant
1
2
3
4
CVR
1
5**
0.429
1
1
5
0.714
Not at
all
Essential
Don't know
Genetic Test Result
Family history
153
10. The DNA sequences of two randomly selected healthy
individuals of the same sex are 90-95% identical.
true false don't know
11. Most common diseases such as diabetes and heart disease
are caused by a single gene variant.
true false don't know Domain:
Competency/ Knowledge cont.
12. The Essential Competencies and Curricula Guidelines for
Nurses in Genetics and Genomics are endorsed as being a
standard part of nursing practice. Have you heard or read
about these Competencies?
Yes
No
Relevancy (1-4)
1- Not relevant
2- Somewhat relevant
3- Relevant
4- Very relevant
1
2
3
4
CVR
3
4
1
1
2
3**
0.428
Relevancy (1-4)
1- Not relevant
2- Somewhat relevant
3- Relevant
4- Very relevant
1
2
3
4
CVR
1
4
1**
-0.714
Relevancy (1-4)
1- Not relevant
2- Somewhat relevant
3- Relevant
4- Very relevant
1
2
3
4
CVR
2
4**
0.714
Relevancy (1-4)
1- Not relevant
2- Somewhat relevant
3- Relevant
4- Very relevant
1
2
3
4
CVR
1
6
0.714
13.
Excellent
Please rate your
understanding of the
genetics of common
diseases
In describing your
genetic/genomic
knowledge, would you
consider it to be
154
Domain: Social System
Conceptual definition: “The environment in which the innovation is being introduced, the
interconnected entities involved in shared problem solving” (Calzone et al., 2012, p. 12).
Contextual definition: Supervisory support for nurses using genomics, and institutional financial support
for genomic continuing education ” (Calzone et al., 2012, p. 12).
Relevancy (1-4)
1- Not relevant
2- Somewhat relevant
3- Relevant
4- Very relevant
1
2
3
4
CVR
2
1
1
3
0.142
2
5
1
1
3
3
0.714
2
5
1
3
4
1
Domain: Decision/Adoption
Conceptual definition: “Observation of use of the innovation” (Calzone et al., 2012, p. 12).
155
Contextual definition: “Utilization of family history within the past three months” (Calzone et al., 2012,
p.12). Use of family history was selected as a measure of adoption because it is independent of
availability of technology and financial resources.
15. In the past three months, how often have you collected a
complete family history from a patient that includes the
following components: information on disorders from three
generations, and age at diagnosis and death for each affected
family member?
Always Often Occasionally Rarely or Never
16. In the past three months, has any patient initiated a
discussion with you about genetics?
Yes
No
Relevancy (1-4)
1- Not relevant
2- Somewhat relevant
3- Relevant
4- Very relevant
1
2
3
4
CVR
7
1
Relevancy (1-4)
1- Not relevant
2- Somewhat relevant
3- Relevant
4- Very relevant
1
2
3
4
CVR
7
1
156
17. Thinking specifically about patients that you have seen in
the past three months, please answer the following
questions.
Relevancy (1-4)
1- Not relevant
2- Somewhat relevant
3- Relevant
4- Very relevant
1
2
3
4
CVR
6**
0.714
2
5
1

157

Appendix
158
F.1
Path Model Using Imputation 1
This path model depicts the relations among variables in the analysis. p* < 0.001; p** =
0.077
F.2
Path Model Using Imputation 2
Social
System
Competency
/Knowledge
Attitudes/Receptivity
Decision/Adoption
Confidence
.
355
*
0.260
*
0
.622
*
-
0.026
**
0
.062
*
-
0.323
*
0.344
*

Appendix
159
This path model depicts the relations among variables in the analysis. p*< 0.001; p** =
0.017
F.3
Path Model Using Imputation 3
Social
System
Competency
/Knowledge
Attitudes/Receptivity
Decision/Adoption
Confidence
.
350
*
0.280
*
0
.659
*
0
.343
*
-
0.035
**
0
.093
*
-
0.325
*

Appendix
160
This path model depicts the relations among variables in the analysis. p*< 0.001; p** =
0.002
F.4
Path Model Using Imputation 4
Social
System
Competency
/Knowledge
Attitudes/Receptivity
Decision/Adoption
Confidence
.
337
*
0.255
*
0
.637
*
0
.337
*
-
0.046
**
0
.072
*
-
0.325
*

Appendix
161
This path model depicts the relations among variables in the analysis. p*< 0.001; p** =
0.010
G
β weight Standardization
Figure 10
SEM β weight Standardization Original Data Set.
Social
System
Competency
/Knowledge
Attitudes/Receptivity
Decision/Adoption
Confidence
.
372
*
0.252
*
0
.628
*
0
.336
*
-
0.037
**
0
.079
*
-
0.325
*

Appendix
162
p* < .001; p** = .013
Although we were unable to arrive at a stable set of model parameters for the CFA, the
final model parameters achieved through the CFA do provide some insight into the relation
between the theoretical latent variables. The standardized root mean square residual (SRMR),
an indication of how well the model fit the data was .062; Hu & Bentler (1998) suggest that
SRMRs of less than .08 indicate an adequate fit the data to the model. Therefore, although we
cannot
Social Systems
Competency/Knowledge
Attitudes/Receptivity
Decision/Adoption
Confidence
.300*
.101*
.407*
.449*
-
.041**
.123*
-
.258*

163
regard the last model computed through the iterative CFA to represent a reliable or definitive set
of model parameters, by conventional standards of structural equation modeling, the model
presents sufficient fit that we may tentatively explore its parameters for insights into the
relations between the proposed latent variables.
Figure 11 presents the β weights between the standardized latent variable scores. We can
review the weights in the model presented in Figure 11 by starting with the strongest relations.
Beta weights indicate the amount of change in a given standardized ‘outcome’ variable for every
standardized unit in the predictor variable(Cribari-Neto & Zeileis, 2009). The effect of
competency/knowledge on confidence had the largest β weight (.449, p <.001). In other words,
for every one-point change in the standardized competency/knowledge score, which is one
standard deviation of change, there is a .449 point change in confidence. Indicating that an
increase in ones’ competency/knowledge accounted for a substantial portion in the increase in
confidence.
The second largest effect was that of social systems on competency/knowledge (β =
.407, p < .001). Social system support significantly affected nurses’ competency/knowledge in
the hypothesized model. In addition, there is a strong effect of social systems on
decision/adoption (β = .300, p <. 001). However, effects of the social system variable must be
cautiously interpreted, because it consists of only five items. Furthermore, the EFA
demonstrated that most of the social system items may be related to other variables and the
method of interpreting social systems effects should be reevaluated in future studies.
Surprisingly, the hypothesized model shows a negative effect of attitude/receptivity on
decision/adoption (β = -.258, p <. 001). By contrast, the literature review describes positive

