


1
CHAPTER 1
INTRODUCTION
In the year 2004 while serving as the pastor of Nyagiki Seventh-day Adventist
Church—2003-2006—one adult member of this church reported to me that she had
visited a voluntary counseling and testing (VCT) center and had tested positive on
HIV/AIDS. This member indicated that she had been overwhelmed with grief when this
sad news was broken to her; “I saw deep darkness before me,” she said. Unfortunately,
she was alone when this news was shared to her and she did not feel safe to share it with
her family members or the people at church as a way of avoiding stigmatization.
My interaction with this member helped me to understand three important facts.
First, HIV/AIDS is real and affects people who are close to me, my church members.
Second, people who test positive for HIV/AIDS often get overwhelmed and need the
support of trained responders. Third, I must stop being a spectator, I must get actively
involved in the fight to eradicate HIV/AIDS. In other words, I resolved to be a solution
and not be part of the problem. The best way to actively participate—I thought—was to
train church members to care for their fellow members who were infected (It is better to
teach people to fish rather than provide fish for them). In 2014—10 years later—I
enrolled to do “Doctor of Ministry in Health-care Chaplaincy” and my project is entitled,
“A Training Program for Members to Minister for HIV/AIDS patients at Nyagiki
2
Seventh-day Adventist Church, Kenya.” In choosing this project, I am helping to fulfill a
dream that has been burning inside me for about 10 years.
Description of the Ministry Context
According to the church records, Nyagiki Seventh-day Adventist Church was
planted in the year 1936 from Nyanchwa—the first missionary church in the entire Kisii
territory—and was organized into a church in in the year 1950. The original church
building was made of mud-bricked walls with a grass-thatched roof. This building
collapsed in 1952 and the members erected a permanent soapstone structure in 1954 with
unique chairs made from concrete cemented bricks. This structure exists up to the present
time—with slight renovations made. Having had over thirty congregations descend from
her, Nyagiki is one of the oldest churches in South Kenya Conference territory and seems
to be going through a plateau stage.
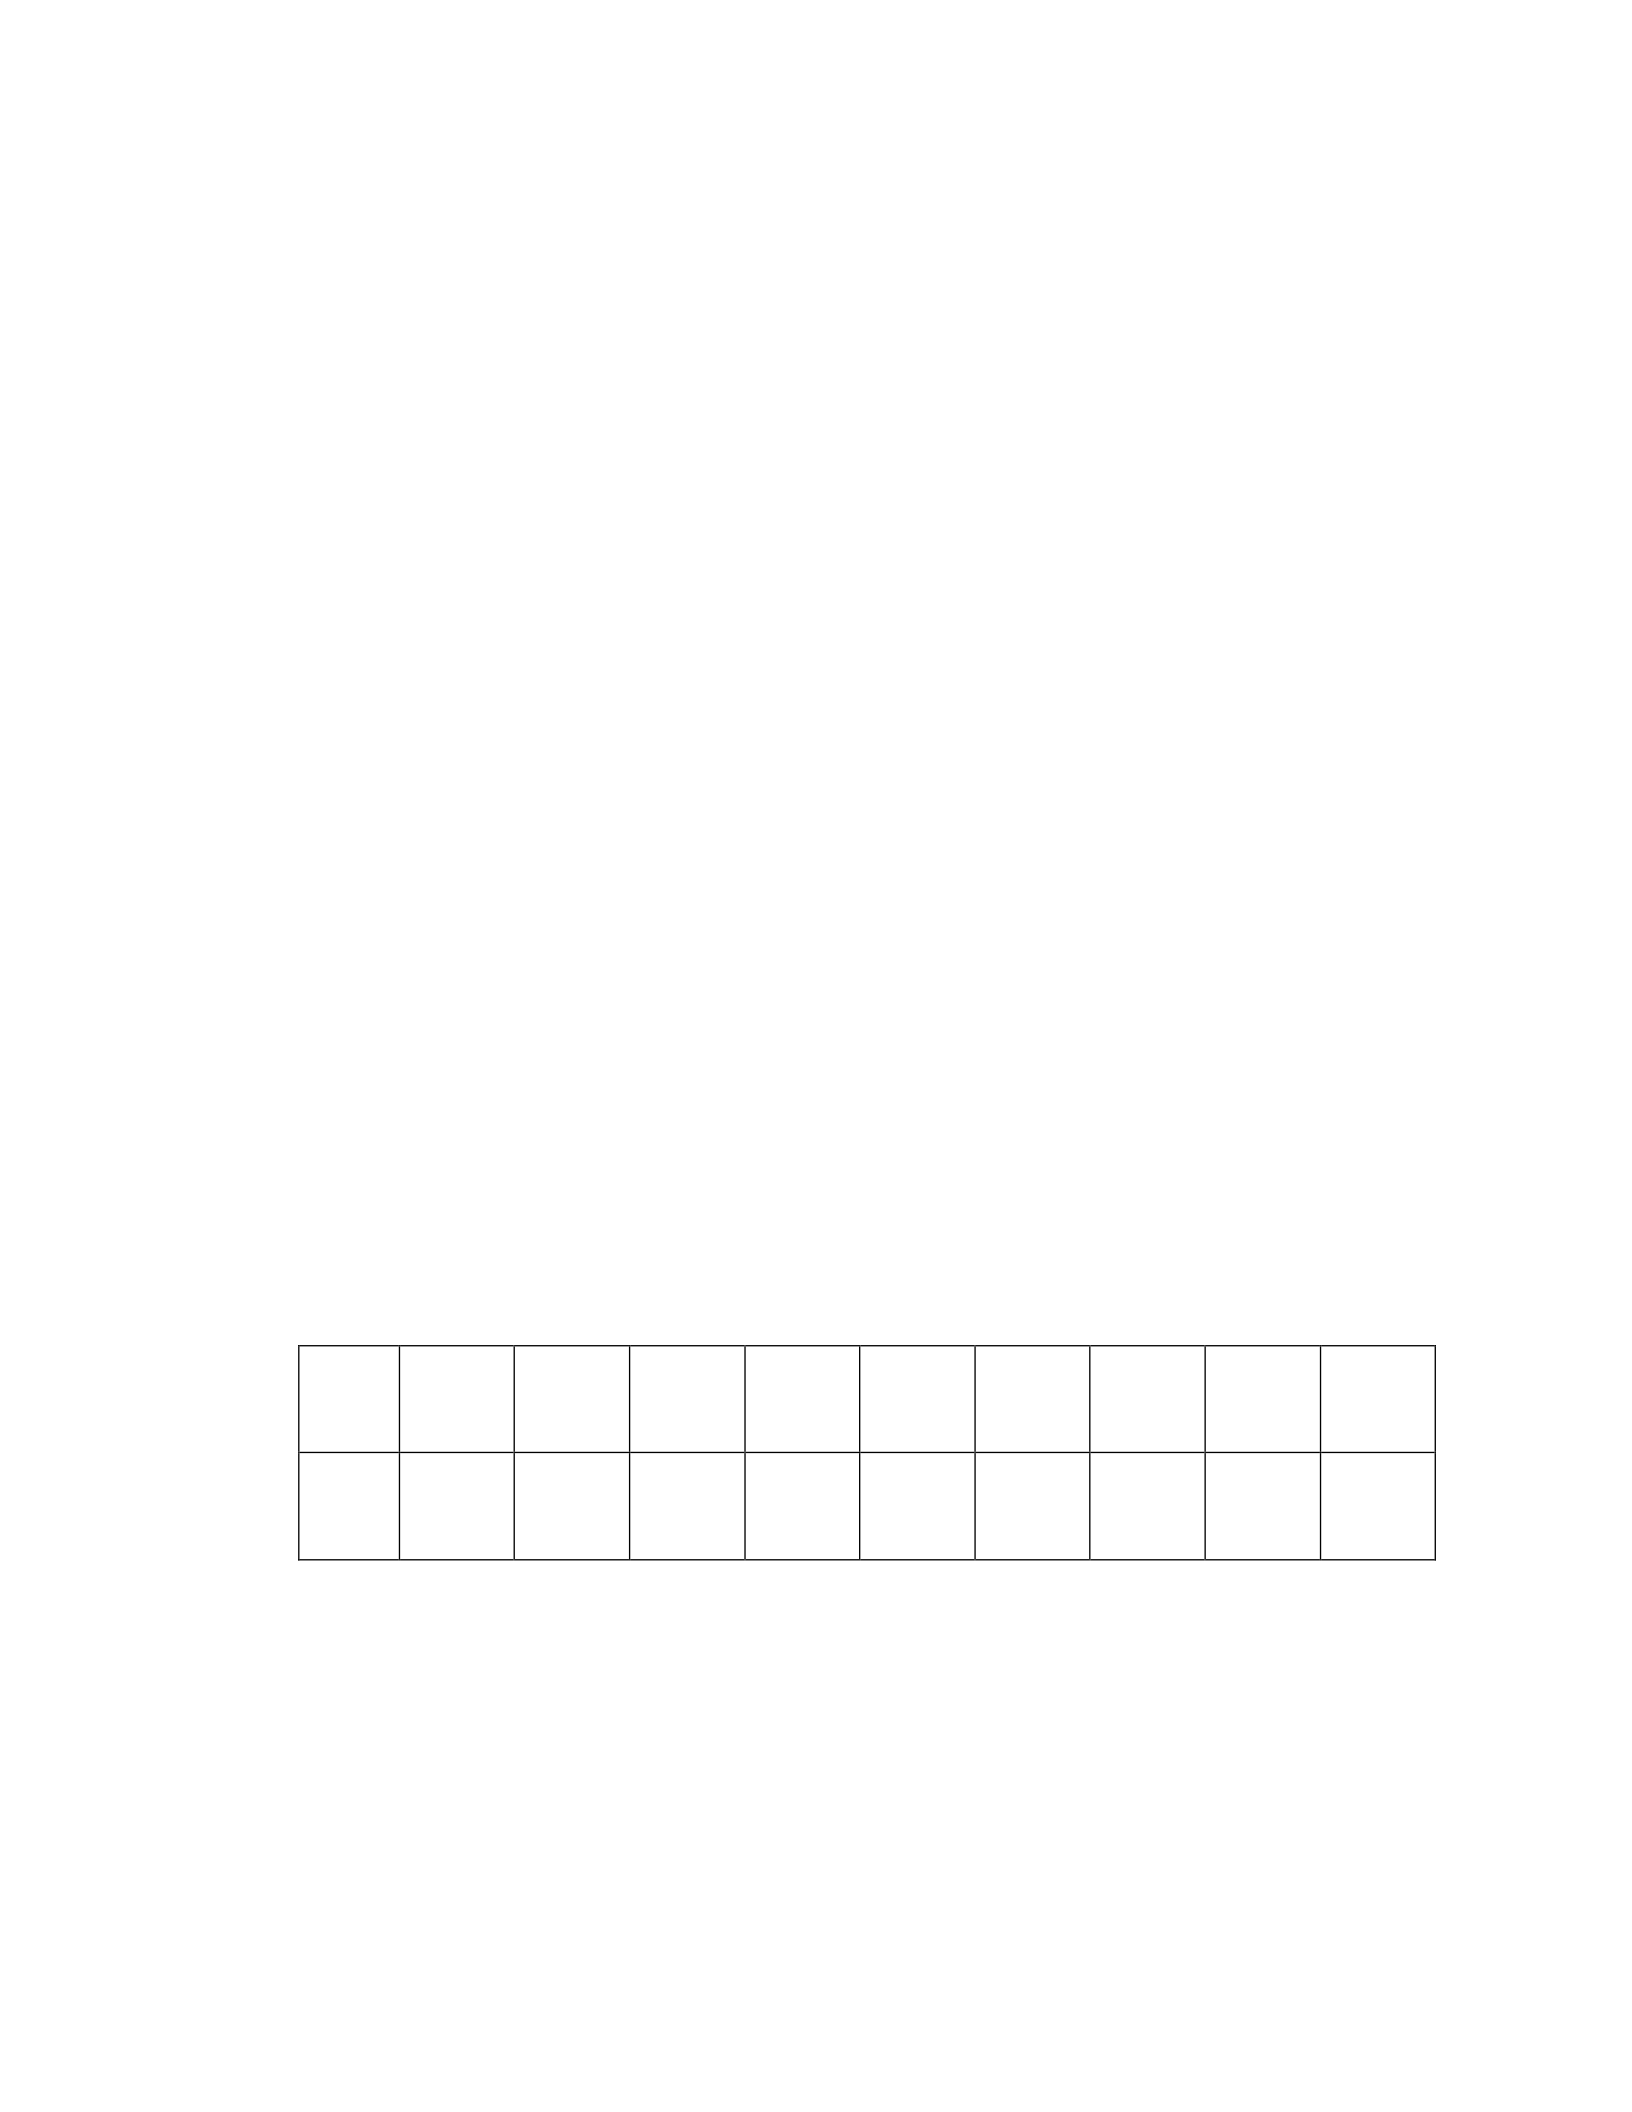
Table 1
Nyagiki Church Membership (2004-2013)
Source: Retrieved with permission from Nyagiki church clerk’s records.
A critical analysis of the Table 1 shows that Nyagiki church membership had
remained relatively constant in a decade (2004-2013). Between 2004 and 2005, Nyagiki
2004
2005
2006
2007
2008
2009
2010
2011
2012
2013
290
205
205
205
188
188
188
181
171
171

3
planted a new church—Nyansongo—and transferred about eighty-five members there (I
was the officiating minister in organizing Nyansongo into a church in the year 2005).
Over all, Nyagiki lost 34 members, in a period of 10 years who are not clearly accounted
for. I served as a pastor of Nyagiki Church for four years (2003-2006). On top of serving
this church, I was also assigned to pastor 19 other churches and 10 companies—making a
total of 30 congregations.
Nyagiki Church enjoys a rural environment close to two cities—Ogembo (three
miles) and Kisii (six miles). Geographically, Nyagiki falls under Nyanza province (there
are a total of eight provinces in Kenya). Nyanza province is leading other provinces in
having the greatest number of people living with HIV and AIDS (PLWHA) (Kalipeni,
Craddock, Oppong, & Ghosh, 2004, p. 177). Under the current constitution—which was
promulgated in 2010—Nyagiki now falls under “Kisii County.” In the year 2004, the
government of Kenya established a modern tea factory—Itumbe Tea Factory—two miles
from Nyagiki Church. The presence of this tea factory in the area is both a blessing and a
curse. It is a blessing because it has provided employment opportunities to people coming
from far and near. It is also a blessing since it has facilitated some social amenities—such
as good roads and electricity—to come to the area and a market for farmers to sell their
produce. It is a curse because it has increased the level of pollution—both environmental
and social. According to the research study done by Kennedy Nyabuti Ondimu, migrant
workers are listed among the risky HIV/AIDS groups given the tendency of some of them
engaging in unprotected casual sex (Ondimu, 2005, p. 72). Ondimu—who conducted his
research among the migrant workers at Kericho tea plantations in Kenya—asserts that
“physically demanding jobs, long working hours, meagre salaries, and crowded living

4
arrangements further promote drug abuse, drinking and promiscuity… most men,
whether married or unmarried, stay alone and are more likely to visit a commercial sex
worker every payday” (Ondimu, 2005, p. 94). Kalipeni et al. (2004) concur with Ondimu
that migrant workers are a risky HIV/AIDS group (this affects both men and women who
migrate to seek employment opportunities or new markets to sell their goods) (pp. 183,
184).
Nyagiki is situated on a hill surrounded by five other Adventist churches and two
companies—within a circumference of about five miles—making a total of eight
congregations. These congregations are shepherded by one senior pastor and one
associate pastor; together they make “Nyansongo Camp Center” (having headquarters at
Nyansongo Church, where a yearly camp-meeting is held, Monday through Saturday).
The following is a list of the eight congregations and their membership as of May 2018:
Nyagiki (192), Nyansongo (268), Riamakora (237), Nyanuguti (182), Chigware (109),
Itumbe Central (162), Matongo II Company (76), and Engoto Company (51). The total
membership is 1,277. It was a great honor for me and the participants to be granted
permission—by the South Kenya conference—to be speakers at this camp-meeting in
August 2017.
Statement of the Problem
During my pastoral experience at Nyagiki, I observed that although HIV/AIDS
was a big threat in the church and society, many of the church leaders were not involved
in addressing this crisis. There were no intentional church training programs to warn the
members about its danger. The church did not make a budget of time or money to address
this pandemic. The root problem that caused this situation was lack of health information

5
literacy on HIV/AIDS to equip these leaders with knowledge and skills to deal with this
crisis.
Statement of the Task
The task of this project was to develop, implement, and evaluate an HIV/AIDS
training program at the Nyagiki Seventh-day Adventist Church to equip the members to
effectively minister to HIV patients in the church and in the community. This research
project was carried out by 24 participants over a period of 1½ years. The participants
were adult members of Nyagiki Seventh-day Adventist Church, South Kenya
Conference.
Delimitation of the Study
This project was carried out by people who are members of Nyagiki Seventh-day
Adventist Church, South Kenya Conference, and were 18 years of age and above.
Participants were chosen from those who are familiar with the cultural context and are
able to communicate fluently in ekegusii dialect. The Ekegusii language was the medium
of communication and efforts were made to translate the materials from the English
language (into Ekegusii language). Being fluent in English was an added advantage (but
not required) given the fact that the books that were used are written in the English
language. Since this project reached out to people living with HIV/AIDS, persons who
have declared that they are HIV/AIDS positive were eligible to be trained, to help protect
their vulnerability and to avoid conflict of interest.
Description of the Project Process
Having the project process was like having a plan for constructing a house.

6
Without a good plan, the construction is doomed to fail. The plan of my research project
included one research question and six chapters. The six chapters are compared to
different phases of building a house.
The Research Question
The research question protects the researcher from getting distracted and losing
the focus. It is like a music conductor who ensures that that all voices in a choir are in
harmony. The research question provides a goal for research and all activities must be in
tune with the goal (Koenig, 2011, p. 75). Similarly, Swinton and Mowat assert that the
research question is an important tool for the researcher; it must be interesting, simple
and modest (Swinton & Mowat, 2006, pp. 54, 55). The research question was developed
to guide the training. The research question in my project was a tool to keep me
motivated and focused and to be an instrument (just like a plumb line in the hands of a
builder) to assess the success of the project. The research question for this dissertation is,
“Naaman found healing for his leprosy in the River Jordan. Can the people living with
HIV/AIDS today find healing in the church?”
The Six Research Project Chapters
Chapter 1 is an overview of the project. It describes the ministry context,
statement of the problem, statement of the task, delimitation of the project, description of
the project process and the definition of terms. It also provides a summary of what each
chapter is all about.
Chapter 2 discusses the theological foundations on how to deal with HIV/AIDS
pandemic. Although HIV/AIDS is not mentioned in the Bible directly, it is often
compared to leprosy. It is often reported that there was no cure for leprosy but there are

7
explicit examples both in the Old Testament and in the New Testament where people
suffering from leprosy received a cure. Naaman is one of those examples (2 Kgs 5).
Naaman was healed when the prophet, Elisha, commanded him to wash himself seven
times at the river Jordan. The case of Naaman will receive an in-depth exploration. In the
New Testament, there are several cases where Jesus healed people who were previously
living with leprosy. However, due to the limitations of this project, the passage of Mark
1:40-45 will be focused.
Chapter 3 reviews relevant literature that talks about HIV/AIDS. Priority is given
to literature giving information about HIV/AIDS in Sub-Saharan Africa and specifically
those that talk about the situation in Kenya. Nyagiki is situated in Nyanza province
(currently known as “Kisii County”) which has the highest number of people living with
HIV/AIDS in Kenya. Most of the books that have been reviewed are those which have
been written after the year 2000. However, to provide a bigger picture, some literature
written in the 1980s and 1990s have also been selected given the fact that the first cases
of HIV/AIDS in Kenya—and most Sub-Saharan Africa—were first reported in early to
mid1980s.
Chapter 4 focuses on the theoretical plan for implementation of the training
program at Nyagiki. The researcher interacts with the education philosophies of Knowles,
Jethro, Maslow, and Jesus Christ. Interacting with these great educators was strategically
important to provide a user-friendly framework for training adults at Nyagiki. From
Knowles, I learned how to interact with the participants acting as facilitator and not as a
lecturer. This approach was effective in keeping the interest of the participants high.
From Jethro, I learned about the wisdom of dividing the participants into small groups—

8
focus groups—and assigning each focus group a territory (zone) to visit. From Maslow, I
learned about how to strive to prioritize the people’s needs. For example, people who are
starving need to be given food before listening to a sermon. From Jesus, I learned the
process of disciple making. Jesus applied a lot of patience transforming his twelve
apostles beginning from the known and ending at the unknown. His teaching strategy
may be summarized as follows: “First, I do you watch me; second, we do it together;
third, you do it I watch you; lastly you do it alone without me watching over you.”
Chapter 5 analyses how the training program was implemented. To successfully
construct a house, the constructor and the builders must be intimately connected. The
researcher is the constructor and the participants are the builders in the research. The
work undertaken by the researcher to implement the training program at Nyagiki included
the following three steps: First, the participants were recruited and signed the consent
forms. Secondly, the researcher provided the objectives of the training to the participants.
Thirdly, the researcher and the participants implemented the objectives which included
reading the book, “ministry of healing,” visiting people living with HIV/AIDS in the
community, meeting in focus groups (and submitting monthly reports to the researcher),
participating in the annual camp meeting, and meeting with the researcher for group
interviews at the end of the training.
Chapter 6 focuses on evaluation and assessment of the training project. During the
creation week, God always looked back at the end of each day to assess the progress
made. The tool for evaluation is the participants’ responses to the six focus questions.
The data was interpreted, and conclusions were drawn from that data. A summary of the
conclusions will be presented for chapters two through five leading to the overarching

9
conclusions. Chapter 6 will also present evidences of my transformation as ministry
professional and will provide recommendations for researchers who may be interested to
do studies in the same field (or in related fields) in the future.
Definition of Key Terms
AIDS stands for Acquired Immuno-Deficiency Syndrome. AIDS causes a
person’s immune system less capable of fighting infections. The word “syndrome” means
that AIDS is not a disease but a condition. “It presents itself as a number of diseases and
symptoms that come about as the immune system fails” (Wanjama, Kimani, & Lodiaga,
2013, p. 3)
Church, according to Wikipedia, the free encyclopedia, the word “church” is used
to refer to the group of people (body of all believers) who are loyal to Jesus Christ both in
a local and in a universal setting. The Greek translation is ekklesia and this word appears
twice in the New Testament and in both instances alluded to Jesus. First, Jesus uses
ekklesia when He told Peter that he was the rock on which he was to build His church
(Matt 16:18), Second, Jesus uses ekklesia in admonishing a wronged person to report to
the “church” after other interventions to make reconciliation have failed (Matt 18:17),
(“Christian Church,” 2018). The word church is used in this research document in an
immediate sense to refer to the local believers at Nyagiki Seventh-day Adventist Church
and in a wider sense to refer to all people universally who believe and follow Jesus
Christ.
Gusii language (also known as Kisii or Ekegusii) is a Bantu language spoken in
the Kisii district in Western Kenya, having headquarters in Kisii town, (between the
Kavirondo Gulf of Lake Victoria and boarder with Tanzania). It is spoken by the Gusii

10
people—one of the tribes of Kenya—numbering about two million (“Gusii People, ”
2018). The members of Nyagiki used Gusii language as official language of
communication. Gusii language is my first language (my “mother tongue”) and it is the
language that I used to interact with the participants and the church members.
HIV stands for Human Immuno-deficiency Virus. “A virus is a tiny particle that
attaches itself to a cell of another creature and uses it to multiply, thereby making copies
of itself” (Wanjama et al., 2013, p. 2). There are many types of viruses, the HIV virus is a
lentivirus, a type that attacks the body’s immune system eventually resulting to the
Acquired Immuno-Deficiency Syndrome (AIDS). Once inside the body, the virus attacks
and destroys types of white blood cells that form part of the human defense system
(Wanjama et al., 2013, p. 2).
Nyagiki Seventh-day Adventist Church is the focus of my research project.
Nyagiki is situated in Kisii County—to the western part of Kenya (about two hours from
Lake Victoria). Nyagiki is a member of sister churches forming the South Kenya
Conference (SKC). According to Adventist online directory, SKC has 830 churches with
a membership of 190,840 (as of June 30, 2017) in a population of 3,095,984 (“South
Kenya Conference-Adventist Organizational Directory,” October 18, 2017).
Pandemic means that the effects are experienced globally—having a worldwide
magnitude as opposed to an outbreak which is localized. As a global pandemic,
HIV/AIDS is one of the greatest challenges of our time. Although some parts of the
world have been affected more than others, every part of the world lives in fear of the
scourge. In Africa, the rates of HIV infections in Sub-Saharan Africa are the highest in

11
the world, with up to 35% of the adult population infected in parts of Eastern and
Southern Africa (Wanjama et al., 2013, p. 1).
Patient according to Wikipedia, the free encyclopedia, was originally used to refer
to any person experiencing suffering, “one who suffers.” The current usage of the word
refers to any person receiving professional medical attention either on a short-term or
long-term basis (“Patient,” 2018, August 28). This word, “patient,” is used in this
research document to refer to people who have professionally been diagnosed with a
condition (in most cases, HIV/AIDS) and are dealing with that condition with or without
the assistance of medical experts.
Qualitative research was chosen for this research project. Qualitative research is
subjective, and the researcher is part of the study. Those involved in the research are
called participants who report their experiences and researcher focuses on interpretation
(Koenig, 2011, pp. 115, 116). The participants form is divided into units called focus
groups who focuses on collecting data. The advantage of qualitative research is that it is
providing data that is rich, detailed, meaningful, salient, and relevant (Koenig, 2011,
p. 124).
Stigma implies the branding or labelling of a person or a group or persons due to
perceived physical, psychological, or moral condition believed to render the individual
unworthy of full inclusion in the community. Because of stigma, some people are treated
unfairly. It is associated with injustice and discrimination. HIV/AIDS patients tend to be
marginalized because this disease is associated with same sex marriages, intravenous
drug usage, commercial sex work, and marital infidelity (Browne, 2016, pp. 13, 14).

12
CHAPTER 2
THEOLOGICAL FOUNDATION IN RESPONDING TO
HIV/AIDS PANDEMIC
Introduction
HIV/AIDS is a serious disease. The suffering that this disease has caused to
humanity in the last thirty plus years of its existence are untold. There are similarities
between HIV/AIDS in the present time and leprosy in the biblical times (Brueggemann,
2000, p. 332). Both are regarded as social diseases and the response to them from the
public have been driven by both fear and ignorance. In as much as there is no permanent
cure for HIV/AIDS now, it is reported that there was no cure for leprosy in the biblical
times. Many people today look down upon HIV/AIDS patients as people receiving
retribution for living sinful lives. In biblical times, society generally associated sickness
with sin. Leprosy was regarded as a contagious disease and lepers were legally isolated to
live separate lives from the general population. Today, there is some tendency to isolate
people living with HIV/AIDS.
God appears in the Bible as a loving person who does not show discrimination.
There is no sinner beyond the reach of God’s arms of love. Jesus made effort to reach out
to outcasts and sinners and to put a smile on their faces. Today if we have love in our
hearts, we will overcome prejudice and we will reach out and touch the untouchables.
With these thoughts in mind, it is reasonable to make a salient statement—that will serve

13
as a theme for this research project—“if our hearts are filled by God’s love, we will touch
people who are filled with suffering.” The first half of this chapter will examine how
Naaman was able to receive a cure for his leprosy. The second half of this chapter will
examine how Jesus healed a man from his leprosy. In both cases, relevant lessons will be
drawn on how to care for people living with HIVAIDS in our present time. Finally,
recommendations for further research will be made leading to a conclusion.
Origin and Definition of Leprosy
Leprosy was present in Egypt and it is here that the Israelites first came into
actual contact with it. When the Israelites left Egypt, God promised to keep them safe
from the tragedy of leprosy and other diseases if they obeyed his laws (Exod 15:26).
1
Unfortunately, Israel was not always obedient to God and we have some specific cases of
people who were afflicted with leprosy because of their sins. These included Miriam
(Num 12:10-15), Gehazi (2 Kgs 5:27), and King Uzziah (2 Chr 26:16-21) (Nichol, 1978,
p. 763). These three persons mentioned here were afflicted with leprosy as a punishment
for sins committed. Miriam was punished for teaming up with Aaron to speak
contemptuously against Moses’ wife (Num 12:1-2). Andrews University Study Bible
(2010, p. 183) argues that Miriam was punished but Aaron was excused because she is
mentioned first (12:1) and it seems that she was the instigator of the criticism against
Moses. Gehazi was punished for coveting against the material goods brought by Naaman
and for bearing false witness (2 Kgs 5:25-27). King Uzziah was punished for the sin of
pride in entering the temple and offering incense (a job that was meant to be performed
1
Unless otherwise indicated, all Bible references in this dissertation are from the New International
Version.

14
by the Levites only). Uzziah was a leper until the time of his death (2 Chr 26:16-21). It is
remarkable to note that Miriam is the only female mentioned by name in the Bible who
had leprosy and she is the only one from the list of three persons mentioned above who
received healing. Her healing came about after Moses had interceded for her. She was
isolated (stayed outside the camp) for seven days before she was received back into the
fellowship of the Israelites (Num 12:13-15).
The word translated “leprosy” is derived from Hebrew word “sara” which means
“to strike down.” Leprosy can, therefore be viewed as a form of a “stroke.” The Jews
regarded a person suffering from leprosy as one smitten of God—a direct punishment
from God for doing evil (Nichol, 1978, p. 763). Leprosy was considered to be the most
terrible sickness and since it was assumed to be contagious, a person suffering from it
was driven from society and was considered as an outcast worthy of little sympathy or
compassion (Nichol, Cottrell, Neufeld, & Neuffer, 1978, p. 761). White (1940) says that
leprosy was the most dreaded disease of all diseases known in the East. It was incurable
and contagious. The victims were considered sinners suffering the consequences of their
sin and they were ritually unclean (p. 262). They were excluded from their homes, from
the cities, from the sanctuary, and from any gathering. If a leper approached another
person, the leper was to cover his lips and shout, “unclean! unclean!” If he/she entered
any house or building, it too became unclean, as did anyone who touched him/her. Nichol
gives an explicit description about the suffering a leper could go through before his/her
final demise. At the onset, the victim could not feel pain or inconvenience. Nevertheless,
the disease gradually developed inside a person. Like in cancer patients, sometime the
leper could experience times of recession when the symptoms could disappear for a

15
season. The picture was awful at the last stage of the disease;
the nose and fingers might drop off, the eyelids disappear, the sight completely
vanishes, and the sufferer looked more like an apparition than a living being. His/her
was a living death. . . . The affliction spread until it reached some vital organ, and
then culminated in the death of the victim. (Nichol et al., 1978, p. 761)
The Levitical Law on Leprosy
Leviticus chapters 13 and 14 extensively describe the laws and regulations on
how to treat lepers. Leprosy is a generic term referring to more than one skin disease such
as psoriasis and vitiligo. In vitiligo, the hairs of the affected part turn white.
According to the Levitical law, once the leprosy disease was confirmed on a person, the
high priest declared that person “unclean.” This person had to tear his clothes and put a
covering upon his/her upper lip and cry, “unclean! unclean!” Because leprosy was
contagious, a leper had to live a separate life outside the camp. “Ostracized from the
community, they were left homeless without the support structure of family and friends”
(“Leprosy,” 2018). Joel Marcus asserts that the situation of a leper was as good as a dead
person; “sufferers were regarded as, in effect, corpses, and physical contact with them
produced the same sort of defilement as touching dead bodies” (Num 12:12; Job 18:13);
(Marcus, 2000, p. 208). Today people who are infected with HIV/AIDS suffer a similar
social isolation (Bock, 1996, p. 156).
The priests played a crucial role like the work done by physicians today. The
priest had the responsibility of examining the suspected person to declare them “clean,”
or “unclean.” If a person tested positive on leprosy, he/she was separated from the
society. If he/she was healed, then that person had to call for a priest who could go there
and examine him/her. If the priest was satisfied that the person had been healed, then the
person was required to go through series of rituals to be set free. The ritual included two

16
stages: one had to take place outside the camp where the person was living and the other
had to take place at the temple where the priests had their “offices.” The rituals included
the sacrifice of animals or birds (Num 14).
To do their work successfully, the priests needed to exhibit a lot of patience and
compassion. “He must learn not to shun the leper but to pity and help him. This is a
lesson for the servants of God today. Like the priest of old, the minister of God today
must have compassion” (Heb 5:2) (Nichol et al., 1978, p. 768). The disease of sin is
compared with leprosy. In as much as leprosy spread slowly but gradually until it
consumed the whole body leading to death, sin also spreads silently in the body and the
victims may not be feeling the pain until the whole body is consumed leading to death.
“So, sin at last comes to fruition, until the image of God in man is practically obliterated.
As leprosy ended in death, so sin ends in death. It would seem, therefore, that leprosy is a
disease especially adapted to typify sin in its various features as no other malady could”
(Nichol et al., 1978, p. 768).
The Healing of Naaman From his Leprosy
Introduction: The Difference Between
“Cure” and “Heal”
There is a difference between the two verbs “cure” and “heal.” Merriam-Webster
dictionary defines “cure” as follows: (a) to make someone healthy again after an illness,
(b) to stop a disease by using drugs or other medical treatments, (c) to provide a solution
for something (Hacker, 2011). The word “heal” is defined as follows: (a) to make sound
or whole, (b) to restore to health, (c) to cause an undesirable condition to end, (d) to patch
up a breach or division between friends, (e) to restore to original purity or integrity
(healed of sin) (Hacker, 2011). Greider (2007) defines “cure” as the absence of illness

17
while “healing” is living with integrity in the face of illness or other suffering (p. 196).
From these definitions, it clear that whereas “cure” has to do with the physical well-being
of a person, “healing” encompasses the holistic well-being: physical, social, mental,
emotional, and spiritual.
James Strong uses the Hebrew word shalom to capture the concept of total health.
Shalom means completeness, wholeness, health, peace, welfare, safety, soundness,
tranquility, prosperity, perfectness, fullness, rest, harmony, the absence of agitation or
discord (Strong, 2007). It refers to a situation where there is total peace to a person and
his/her environment; “shalom as a term and message, seems to encapsulate a reality and
hope of wholeness for the individual, within societal relations, and for the whole world.
To say joy and peace, meaning a state of affairs where there is no dispute or war, does not
begin to describe the sense of the term” (Shalom, 2015). Shalom is related to the Arabic
root salaam, which means to be safe, secure, and forgiven, among other things. “Salaam
is also the root for the terms “Muslim” (and Islam), literally translated, he/she who
submits to God and submission to God, respectively”(Shalom, 2015). In the Latin and
Romance languages, shalom is translated to mean “peace.” “Peace” is viewed as an
important possession in personal, social, political, and religious avenues. The Greek word
for peace is Eirene which means quietness and rest (Shalom, 2015).
Exegesis on 2 Kings 5:1-27
The New Interpreter’s Bible describes Naaman as a great man, Issaagadol (Keck,
1995, p. 193). Naaman is favored by the King of Aram (ancient Syria) because of his
successful military campaigns against Israel, perhaps referring to the Aramean victory
over Ramoth-gilead (1 Kgs 22:19-23). In spite of his great accomplishments and

18
greatness, Naaman has a terrible skin disease which has a social stigma and is associated
with death (Num 12:10-12) (Keck, 1995, p. 193). Although many translations retain the
word “leprosy,” when describing Naaman’s medical condition, “most scholars now agree
that the Hebrew word does not refer to leprosy as we know it today (Hansen’s disease),
but to a skin afflictions of various sorts, here probably psoriasis or vitiligo” (Keck, 1995).
Mike and Tara Campbell help us understand the text. They say the Hebrew meaning of
the name “Naaman” means “Pleasant” or “beautiful, delightful” (Campbell & Campbell,
2015). Naaman was a Syrian (Aramean), the commander-in chief of the armies of
Benhadad (Syria). At this time, Joram was the King of Israel which had its capital city in
Samaria. Elisha was a prophet of God residing in Samaria. Despite his prosperous
personal and public life, Naaman was afflicted with leprosy. No help had come on his
way until the slave girl who waited on Naaman’s wife revealed that there was a prophet
of God in Samaria who could help. Naaman obtained a letter from Benhadad (King of
Syria) and proceeded with it to Joram (King of Israel). Joram suspected Naaman of
coming with evil motives against him and rent his clothes. The situation changed when
Elisha invited Naaman to come and meet with him. Naaman was healed of his leprosy by
dipping himself seven times in the River Jordan according to the word of Elisha. This
miraculous healing is mentioned by Jesus in Luke 4:27 (Campbell & Campbell, 2015).
Love Overcomes Injustice
Although the name of Naaman means “pleasant,” his behavior in keeping a little
girl captive in his home was no doubt unpleasant. The Seventh-day Adventist Bible
Commentary describes it as a “cruel endeavor” (Nichol et al., 1976, p. 875). It is hard to
imagine the suffering the girl went through in being separated from her family, her

19
friends, and her familiar environment. Furthermore, the fact that she is working without
any salary—being a slave girl—aggravates the situation. Yet, the little girl is described as
resilient and compassionate. Rather than repaying evil with evil, she overcomes evil with
good. “But even in an alien land God had service for her to perform” (Nichol et al., 1976,
p. 875). She offers a way for her master to receive cure for his leprosy.
Nichol asserts that love is a powerful force that delivers healing to Naaman. The
healing is a product of someone whose heart was filled with love; “Filled with love
towards her God, her heart went out in sympathy to her ailing master and his wife.
Instead of wishing Naaman ill because of the misfortunes that had been brought upon her,
she wished him well and hoped for his recovery from his terrible disease (Nichol et al.,
1976, p. 875). The acts of mercy and kindness that Naaman received at the hand of the
little maid are sharply contrasted with the reaction of the King of Israel, Joram. A person
cannot give what he or she does not have. Joram was not filled with the love of God. He
was not living in close connection with God. Joram was filled with fear and despair and
that is what he gave to Naaman (p. 876). Elisha stepped in to rescue Joram from the
embarrassment of failure and defeat. In the New Testament, after the transfiguration,
Jesus too stepped in to save the disciples from the embarrassment of failing to heal an
epileptic boy (Matt 17:14-18).
Love is a force that compels Elisha to desire for Naaman to receive healing.
Furthermore, Elisha desired for Naaman to be acquainted with this love and to take it
back when he would return to Syria. Elisha desired for him to receive more than a cure.
But Elisha asked that he come to him to find healing of body and restoration of soul.
The prophet was anxious that Naaman become acquainted with the love and power of
Israel’s God, and that he take back to his own people a message of comfort
concerning the hope that all might have in him. (Nichol et al., 1976, p. 876)

20
Elisha’s prayer seems to have been answered judging from Naaman’s confession:
“now I know that there is no God in the entire world except in Israel” (2 Kgs 5:15).
Naaman became acquainted with the creator’s wonderful love and care. Healing for
Naaman was the most precious thing that he needed, and he was willing to part with his
possessions for having received that gift. Elisha did not accept any payment for healing
Naaman. Elisha knew that God was the great physician; he was only an instrument in
God’s hands. Therefore, Elisha sent Naaman away with a word of blessing, “go in peace”
(shalom). The message of peace that Naaman received is similar to the message of peace
contained in Jesus’ farewell to His disciples (John 14:27) (Nichol et al., 1976, p. 878).
Naaman had received more than a cure for his sickness. “He was like a new convert to
God filled with joy and peace in his heart, healed of leprosy and converted in spirit”
p. 878).
Gaebelein and Douglas concur with Nichol et al. about Naaman’s changed life.
The act of Naaman descending from his chariot to listen to Gehazi is a mark of humility.
When Naaman first arrived in Israel, he was expecting great things. He was disappointed
when Elisha told him to bathe in the small muddy river of Jordan. In pride, he mentioned
that the rivers of Syria were much bigger and cleaner than this one. After his healing,
Naaman was no longer proud and arrogant, but grateful, reverent, and humble (Gaebelein
& Douglas, 1984, p. 190). Naaman was able to relate better with other fellow human
beings. Before his baptism at the river Jordan, he expected Elisha to come out of his
house and stand before him. After his baptism, he is the one that stands (amad) before
Elisha ready to bless him (Keck, 1995, p. 195). A huge transformation takes place in the
body of Naaman. It resembles the flesh of young boy (na’arqaton) “baby flesh.” This

21
childish young stage is compared to the young and innocent life of Naaman’s servant
(naarahQetannah) (Brueggemann, 2000, p. 334).
Whereas Naaman went from the house of Elisha without Leprosy, Gehazi
(Elisha’s servant) went from his house with leprosy. Nichol et al. (1976) say that the
reason why this happened was because Gehazi’s heart was under the control of Satan. He
was thinking about showing revenge for all the evil that the Syrians had brought to Israel.
Gehazi is great contrast to the little girl, who referred to Naaman as “my master.”
Gehazi’s heart is full of prejudice judging from the way he referred to him: “Naaman, this
Aramean,” (5:20) (Keck, 1995, p. 198). Gehazi thought that he would be justified to
receive gifts from Naaman as part of the payment for all the evil that the Syrians had
brought to Israel (Nichol et a., 1976, p. 878). Gehazi went forward asking God to bless
his sinful mission, “as surely as the Lord lives, I will run after him and get something
from him (2 Kgs 5:20). Gehazi has sown evil and reaped evil: Elisha goes on to name the
things that Gehazi has not taken: fields of olives and vineyards, sheep and cattle, and
servants. Elisha was reading Gehazi’s mind to know the things he intended to do with the
money that he had looted. The sin of Gehazi is deception, unbelief, greed, theft, and envy
(Konkel, 2006, p. 431).
Elisha pronounces a curse to Gehazi; “Naaman’s leprosy will cling to you and to
your descendants forever” (5:27). The word used forever (le’olam) does not mean time
without end but it means that the punishment was irreversible. The curse extends to us
today to those whose hearts are filled with arrogance and covetousness, those who cause
suffering to others in the name of God; “Elisha’s words of rebuke were not only for his
servant Gehazi but those in God’s church today who manifest the same spirit as did

22
Gehazi (Nichol et al., 1976, pp. 879-880). This text gives a stern warning to opportunists
like Gehazi who are ready to make a quick profit in the name of the Lord (Keck, 1995,
p. 198).
The Relevance and Application of the Story of
Naaman to HIV/AIDS Patients
Response driven by love. There are two parties that emerge from the HIV/AIDS
patients: The guilty and the innocent. The guilty are those who feel that they are to blame
for acquiring the virus. This would be through their promiscuous lifestyles. The innocent
party are those who see that they have acquired the virus through other peoples’ default
or accident. To respond by love means that one party will not seek ways to spread the
virus to another party whether they are innocent or guilty. Both must never fall into “I
don’t want to die alone” mentality.
Transparence and honesty. It is vitally important for married couples to be
transparent to each other. They should both be encouraged to go for voluntary counseling
and testing and share the results with each other. Doing so can save a life especially in a
situation where one spouse tests positive and the other tests negative (the one who tests
positive can use condom and avoid infecting the spouse who tests negative).
HIV/AIDS patients need healing and not merely a cure. When we understand that
healing (Shalom) means more than physical health; it includes emotional and spiritual
health, then we are safe to say that there is a cure for HIV/AIDS. This can be said of the
people who are at peace with God and their fellow human beings, people who are strictly
following their doctors’ prescriptions and they are able to attend to their daily obligations.
Obey the call to receive help from the hospital. Naaman obeyed the call to go and
receive help by dipping himself in the muddy river of Jordan seven times (It is unlikely

23
that he would have received this help if he had decided to disobey.) It is important for
HIV/AIDS patients to seek for medical help though it may appear humiliating to them.
Encourage the youths to be driven by love and not by wealth. The story of
Naaman captures the character of two young people. One is the unnamed little girl who
championed the decision for Naaman to go to Samaria to seek help. The other young
person is Gehazi who because of his covetousness harvested the leprosy of Naaman. This
story should encourage young people to be modesty in their lifestyle and avoid falling
into the trap of materialism. It is unfortunate to learn that some young people have fallen
into the “sex for money” trap.
The church can play a greater role than the government of the day in caring for
PLWHA. Both the heads of the states of Syria and Israel could not provide a cure to
Naaman for his leprosy despite their wealth. While the king of Syria provided a letter and
financial resources to Naaman, the King of Israel (Joram), appeared desperate and
judgmental (Joram reasoned that Naaman’s body had been fixed by God and there is
nothing else he could do). Elisha, sensing Joram’s desperation, said “let him come to me”
(2 Kgs 5:8). Elisha was able to heal Naaman because he depended on God. By totally
depending on God—with less or no financial resources—the church today can provide
healing to PLWHA.

24
Jesus Touches a Leper (Mark 1:40-45)
Introduction
Jesus is a role model on how to care for people who are sick. Ellen White
describes his method as follows: “The savior mingled with men as one who desired their
good. He showed His sympathy for them, ministered to their needs, and won their
confidence. Then He bade them, “follow me” (White, 1942, p. 143). Furthermore, White
encourages Christ’s followers to use the same method in reaching out to people who are
sick—to use less time in sermonizing and more time in personal work; “accompanied by
the power of persuasion, the power of prayer, the power of the love of God, this work
will not, cannot, be without fruit” (pp. 143,144).
Nichol et al. (1980) say that there was no recorded instance of a person getting
healed from leprosy between the time of Naaman and the time of Jesus (a period of 800
years). The Jews in the time of Jesus regarded leprosy as a divine judgement on sin. The
only known remedy was isolation. A leper was seen as a person under a curse from God
and was abandoned by God and by human beings (Nichol et al., 1980, p. 573). Leprosy in
Jesus time is associated with the present Hansen’s disease;
As the disease progresses, pain turns into numbness, and the skin loses its original
color and becomes thick, glossy and scaly. Sores and ulcers develop, especially
around the eyes and the ears, and the skin begins to bunch with deep furrows between
the swelling and the face of the afflicted individual looks similar to that of a lion
(“Jesus Cleansing a Leper,” 2015).
The first account of leprosy healings by Jesus is recorded in three Gospel books
(Mark 1:40-45; Matt 8:24; Luke 5:12-16). Mark’s account is more detailed (Nichol et al.,
1980, p. 573). Later Jesus healed other leprosy victims (Matt 26:6; Luke 7:22; 17:12-14)

25
and he sent out his disciples to do the same (Matt 10:8). Nichol et al. (1980) give a major
commentary on the Mark’s account.
In Mark 1:40-45, a leper approached Jesus and begged him to heal him. Jesus
reached out his hand and touched the man. “I am willing,” he said. “Be clean!”
Immediately the man was healed, and Jesus commanded him to go and show himself to
the high priest (Mark 1:44). Marcus gives a strong clarification that the nature of the
ailment of this man, though most English translations use the word “leper,” this is not
correct when we compare it with today’s Hansen’s disease (Marcus, 2000, p. 205).
Marcus contends that the Hebrew word sara’t has incorrectly been translated into Greek
as lepros, and into Septuagint as lepra. “The Hebrew term Sara’at/lepra designates a
variety of conditions in which the skin becomes scaly, but not what today is called
leprosy (Hansen’s disease). As described in Leviticus 13-14, “the ailment is one that
develops quickly, and people sometimes recover from it; leprosy on the other hand,
develops over a number of years and is incurable apart from modern drug therapy”
(Marcus, 2000, p. 205). Consequently, Marcus translates Mark 1: 40 as “the man with
scale-disease came up to him” (Marcus, 2000, p. 205). Gaebelein and Douglas (1984)
concur with Marcus that the word “lepros” is a generic terminology used in biblical times
to designate a wide variety of serious skin diseases. “It was not limited to what we know
as leprosy, or, to use the preferable medical term, Hansen’s disease” (Gaebelein &
Douglas, 1984, p. 630). Although it is not known the kind of skin disorder the man was
suffering from, it is apparent that it caused much suffering to him both physically and
spiritually (Gaebelein & Douglas, 1984, p. 630).
The leper in the story had to overcome three obstacles in order to receive healing

26
(Nichol et al., 1980, p. 573). First, there was no known precedence of a person who had
been healed by Jesus since the last healing had taken place in the remote past, 800 years
before. The second obstacle that the leper faced was the popular belief that he was under
the curse of God and therefore Jesus might not heal him. The third obstacle presented a
physical problem: how could he get near enough to Jesus to present his requests? The law
required lepers to keep distance from the “clean” people. It is worth noting that the leper
overcome all the three obstacles and was able to make his request before Jesus. He came
directly to Jesus and knelt down on his knees to make his plea. Darrell (2005) contends
that the way the leper approached Jesus with confidence was an act of faith. He knew that
Jesus was able to grant his request. He made the request without any presumption; “if you
are willing” (Darrell, 2005, pp. 415-416).
Mark 1:41: Moved With Compassion
According to White (1940), Jesus expresses love and compassion to the leper by
his act of stretching his hands and touching the leper. Jesus could have just pronounced a
word and healing would have taken place, but he rather chose to touch him to show
compassion. Whereas the Pharisees despised other people and set themselves aloof from
the sick and the needy, Jesus showed love and compassion (White, 1940, p. 267). In
comparison, Darrell (2005) asserts that the correct translation of the original text should
read that Jesus was moved with compassion and not anger. This is further demonstrated
by the symbolic touch, “Jesus’ power to cleanse was greater than the leprosy’s power to
stain” (pp. 415-416). Gaebelein and Douglas (1984) take a different interpretation; they
argue that the Greek word in verse 41 is orgistheis (“being angered”). Therefore, Jesus
became angry, but his anger was not directed to the man or the disease but to Satan the

27
source of all human suffering. It was Jesus’ mission to destroy the demonic powers and
this mission always brought Jesus into open conflict (Gaebelein & Douglas, 1984,
p. 630).
Mark 1:43: A Stern Warning
Another terminology that seems to be a point of contention is the word
embrimaomai (to speak harshly, to “speak with a strong warning”). This terminology is
used in the context of Jesus sending the healed person to go out (ekballo) and show
himself to the priest. Gaebelein and Douglas (1984) argue that Jesus was not being harsh
to the healed leper as a person. Jesus was expressing his feelings against the act of
disobedience, which he knew that this person was going to commit, and which was going
to make it difficult for Jesus to do his work openly. This act of Jesus where he shows
hatred for sin but love to sinners is what Gaebelein and Douglas call “righteous
indignation” (p. 630). According to Darrell (2005) the strong warning is directed to the
public. Jesus warns the public not to proclaim abroad the miracle which he had
performed while he sends the man who had been healed to go and show himself before
the priest (p. 416). Keck (1995) gives a different interpretation of verse 43. He interprets
the Greek word “ekballo” as “drive away” or “cast out.” Jesus is not driving the person
away from him but the demons that had possessed the man. Hence the violent emotional
response in verse 43 seem more appropriate to an exorcism, casting out demons from a
person to make him free (p. 545).
Mark 1: 45: But the Man Went and
Spread the Word
The healed man is full of excitement and he goes everywhere telling everybody
the great things that Jesus had performed in his life. Marcus sees the healed man as a

28
prototypical missionary. He goes everywhere proclaiming the good news of his healing
which makes others to come to Jesus the way he had done earlier (Marcus, 2000, p. 210).
Darrell (2005) interprets the Greek word used kerusso as proclaiming or preaching.
Having been with Jesus prepares the person to preach/testify about what Jesus had done
to him. This prefigures the work that we are to do today when we receive salvation (We
need to go everywhere to proclaim the good news to make other people to come to
Jesus).
Analysis of Jesus’ Healing Ministry
The leper regards himself as ritually unclean as opposed to physically unclean
(Marcus, 2000) and he petitions Jesus to give him cleansing. The Greek word that the
leper uses is katharizo, “to cleanse,” and not therapeuo, “to heal,” “to cure” (Nichol et
al., 1980, p. 573). In both the Old Testament and New Testament times victims of leprosy
were spoken of as “unclean,” needing “cleansing,” rather than “sick” needing “cure.”
This distinction in terminology reflects the idea of ritual cleansing (Nichol et al., 1980, p.
573). The cleansing of the leper was a response to an act of faith in Jesus’ healing power:
“If you want to, you are able to cleanse me” (1:40b). His usage of the word dynasai (you
are able to) indicates the leper’s belief that Jesus has powers to do what is impossible for
human power (Marcus, 2000, p. 209).
Both the leper and Jesus violated the Levitical law for coming close to each other
in a conversation and for Jesus touching the leper. The act of Jesus stretching his hand to
touch the leper is described as being “deliberatively provocative” (Marcus, 2000, p. 206).
It overlooks the Jewish Levitical law in Leviticus 13-14. It also contrasts with 2 Kings
5:1-14 where Elisha avoids contact with the man whom he cures of scale disease

29
(Marcus, 2000, p. 206). Jesus often touched the sick in healing (Matt 8:15). Jesus is our
role model on how we can touch the untouchables; “He knew that touching a leprous man
meant uncleanness; nevertheless, he did so boldly” (Nichol et al., 1980, p. 573). Jesus
risked contracting ritual impurity himself. “But instead of impurity passing from the man
to Jesus, purity of Jesus’ holiness passes from him to the man, and the latter is cured
(Marcus, 2000, p. 209). The ritual cleansing that Jesus performed to the leper symbolized
the spiritual cleansing that Jesus is able to provide for people sick of sin; “Jesus had come
to the earth for the specific purpose of cleansing sinners, whose spiritual illness was more
deadly than leprosy” (Nichol et al, 1980, p. 573).
That Jesus cleansed this leper from his uncleanness gives evidence that Jesus had
divine powers. Jesus has powers to cleanse souls from sin (Nichol et al., 1980, p. 573).
Despite his divine powers, Jesus had respect for the human laws. He charged the person
who had been cleansed from leprosy to go and show himself to the priests according to
the laws of Moses (Nichol et al., 1980, p. 573). According to the Mosaic Law, the priests
who served as public-health officers diagnosed leprosy and ordered segregation. Those
who recovered from their disease could return home after reexamination, purification
rites, and presumably certification (Nichol et al., 1980, p. 574). By sending this man to
the priests, Jesus was showing to them that he had respect and recognition to the laws that
he himself had imparted to Moses long before. In this way He hoped to disprove the false
charges made by the priests that Jesus did not care about the law of Moses (Nichol et al.,
1980, p. 574). In modern times, it is important to give encouragement to the people who
are sick to go to health facilities to seek medical attention.

30
Emulating Christ in Ministering to the
Needs of HIV/AIDS Patients
Keck (1995, p. 546) asserts that today we are guilty of practicing social isolation
to HIV/AIDS and cancer patients the way the Jews did to lepers in the past. Just at the
time they need to have a loving touch, a hug, a hand to hold, or a pat in the back from a
family member or a friend, they experience distance and isolation instead. The situation
becomes worse when their medical conditions grow into critical stages. Some of them
become completely deserted:
We may no longer confine persons with highly communicable diseases to isolation,
but the subtle forms of social isolation we practice can be just as devastating. Jesus
did not cut himself off from the leper. Instead, he healed the man by reaching out to
touch him. (Keck, 1995, p. 546)
The Wikipedia (HIV/AIDS, 2014) speaks strongly against all forms of
stigmatization against people living with HIV/AIDS. Some of the common practices of
stigma that must be avoided include ostracism, rejection, discrimination, and avoidance.
People must be trained to change their attitudes and behaviors to people living with
HIV/AIDS. Some wrong behaviors include compulsory HIV testing without prior
consent or protection of confidentiality, the quarantine of HIV infected individuals and in
some case the loss of property rights when a spouse die. All forms of violence must be
stopped when dealing with HIV/AIDS patients because these raise fear in their hearts and
makes them to avoid seeking for help that they need (HIV/AIDS, 2014). A research that
was done in Kenya among pregnant women revealed that the violence and stigma that
these women experience from their husbands was a major cause of their refusal to go for
HIV testing (Turan et al., 2011).
Garland (1996) asserts that those who are called by Christ’s name (the church)

31
need to minister to the untouchables of society. They need to possess a non- judgmental
spirit the same as the one Jesus had. They should reach out to HIV/AIDS patients without
seeking to know how they got infected. Christians must be followers of Christ and must
be people who are filled with compassion. They must banish a “holier than thou,” self-
righteous attitude from their hearts. It is wrong to assume that HIV/AIDS is only
transmitted by sexual contact. The fact is that there are a many people who are
HIV/AIDS positive who got infected through other means apart from sexual contact.
Some of the examples of infection are: blood transfusion, breastfeeding, (mother to
child), through infected needles (Garland, 1996, pp. 88, 89). Garland gives reference to a
pathetic story of a pastor named Jimmy Allen whose four members of his household were
infected with HIV/AIDS through other means outside sexual contact. The strange thing is
that their church could not give the needed support and instead they recommended for
pastor Allen to resign from his position (Garland, 1996, pp. 88, 89).
The church has a responsibility of extending the healing ministry of Jesus to the
world that is full of sickness. It is true that there are many people suffering from the
consequences of their sin. It is possible to have people suffering from HIV/AIDS due to
sexual misconduct. The role of Christians is not to increase stigmatization or
condemnation. Already many of the people know those facts and they do not need to be
reminded about them. Rather than reminding people of their sins, the church members
need to remind people of the forgiveness that we have in Christ. Let them know that this
forgiveness has no limits or boundaries. There are people in the church who have the gift
of healing and should use that gift to minister to sick people without giving credit to
themselves. The rest of the church members can be involved in doing intercessory

32
prayers for the sick people. God is still in the business of working healing miracles to his
people today. Church members should not place limits on God regarding healing. Every
church member should be engaged in doing intercessory prayer on behalf of sick people
(Garland, 1996, p. 91).
Conclusion and Recommendations
In this chapter, I have analyzed the plight of lepers in both the Old Testament and
the New Testament times. I have used two cases (one in the Old Testament and another
in the New Testament) to argue my points. Although it was often reported that leprosy
had no cure and was contagious, I have given several examples to prove that this was a
misconception (myth) and not the truth. The truth is that the word leprosy was a generic
terminology used to refer to many skin diseases. Some of them were curable and non-
contagious.
The case of Naaman in the Old Testament seems to fall into this category.
Naaman is evidently seen interacting with several people and no instance is mentioned of
him inflicting the sickness to them. The same applies to the leper in Mark 1: 40-45. It
ends up that the sickness is not physical but spiritual (ritual). Getting sick was viewed by
many as being punishment for sin committed. Ritual sickness calls for spiritual cleansing
which is solely the work of God. Only God can forgive sins. It is a sad situation to realize
that most of the people who were believed to be having leprosy were isolated from the
people who were regarded as clean. The Bible says that all human beings have sinned and
run short of the glory of God (Rom 3:23). Therefore, no person should be at the
judgement seat to pronounce other human beings as more sinful than he/she. In other

33
words, all human beings are ritually unclean and need cleansing that only God can
provide.
The modern terminology used for leprosy is “Hansen’s disease” This sickness is
currently curable and poses no threat to anybody. The modern equivalent of leprosy is
HIV/AIDS. HIV/AIDS currently has no permanent cure. This fact does not give anybody
the license to mistreat the people diagnosed with HIV/AIDS. It is true that many people
suffering from this disease are exposed to a lot of stigma. In this chapter, I have asserted
that people living with HIV/AIDS deserve a fair treatment. This can be possible if we
follow the example of Jesus who was always committed to treating sick people with love
and compassion. This is doable if we have love in our hearts. In harmony with the theme
of this project, “if our hearts are filled with God’s love, we will touch people who are
filled with suffering.”
In sum, for the church to be effective in ministering to the needs of HIV/AIDS
patients, she must emulate three things that Jesus used in healing the leper. First, the
church must be ready to touch—physically and emotionally—people suffering from
HIV/AIDS (however, to prevent infection, it is always wise to follow contact precautions
as directed by the patient’s physician). A proper touch or pat on the shoulder of a patient
is a powerful way to express love. Care providers should first seek permission from the
care-recipients before this ministry is applied. Secondly, the work of the church is not to
substitute but to complement the work of the physicians. Just as Jesus referred the leper
to go and show himself to the priest, the church should always be ready to send patients
to receive medical care as needed. It is important for care providers to be aware of their
limitations and refer their patients to receive help from other professionals. Thirdly, Jesus

34
rebuked demons/sin, but he loved the sinners. The church ought to do the same. While it
may be okay to wisely warn and rebuke sin, church members must unconditionally
extend love and mercy to people who are struggling with sin. Fourthly, it is important for
church members to seek for the forgiveness of the people who are living in sin. Both
Moses and Jesus wrestled with God to extend forgiveness to the people who had sinned
against them.

35
CHAPTER 3
LITERATURE FOCUSED ON HIV/AIDS IN KENYA
Introduction
Literature relating to HIV/AIDS is diverse. For the last 30 years, HIV/AIDS has
been one of the most serious public health concerns throughout the world. Despite great
scientific research and experimentation, there is no permanent cure for this disease. The
academic platform has been flooded with a lot of literature about this killer disease. Time
and space will not allow to review all the literature that has been produced on this
sensitive topic. I will concentrate my effort to review literature dealing with the following
three major topics: (a) Health Information Literacy on HIV/AIDS, (b) Prevention of
HIV/AIDS, (c) Care and Support for People infected and affected by HIV/AIDS. Most of
the works cited are those published after the year 2000. However, to have a bigger
picture, I have also included literature published in the 1980s and in the 1990s (the first
cases of HIV/AIDS were reported in the early 1980s). The context of my study is Nyagiki
Seventh-day Adventist Church, South Kenya Conference. Literature that is focused on
Kenya and sub-Saharan Africa will be given special consideration.
Health Information Literacy
The people’s knowledge of health information is generally low. A study of 2,600
patients conducted in 1995 by two United States hospitals found that between 26% and

36
60% of patients could not understand medication instructions, a standard informed
consent or basic health care information (Health Literacy, 2014). Health literacy is the
ability to obtain, read, understand and use healthcare information to make appropriate
health decisions and follow instructions for treatment. Research show that up to half of
patients cannot understand basic healthcare information. Low health literacy reduces the
quality of treatment and increases the risk of medical error. Various interventions, such as
simplified information and illustrations, avoiding jargon, “teach back” methods and
encouraging patients’ questions, have improved the people’s level of health literacy.
Health literacy is a major concern for health professionals, as it is a primary factor behind
health disparities. The Healthy People 2020 initiative of the United States Department of
Health and Human Services has included it as an urgent new topic, with objectives for
addressing it in the decade to come (Health Literacy, 2014).
Biomedical Approach
The biomedical approach to health literacy that became dominant (in the United
States) during the 1980s and 1990s often viewed individuals as lacking, or “suffering”
from, low health literacy, assumed that beneficiaries are passive in their possession and
reception of health literacy, and believed that models of literacy and health literacy are
politically neutral and universally applicable. This approach is deficient when placed in
the context of broader ecological, critical, and cultural approaches to health; it has
produced, and continues to reproduce, numerous correlational studies where there are
adequate levels of health literacy. The people that have sufficient knowledge and skills
and where members of a community have the confidence to guide their own health,

37
people are able to stay healthy, recover from illness and live with disease or disability
(Health Literacy, 2014).
McMurray states that health literacy is important in a community as it addresses
health inequities, as those at the lower levels of health literacy are often the ones who live
in lower socio-economic communities. Being aware of information relevant to improving
their health, or how to access health resources creates higher levels of disadvantage. For
some people, a lack of education and health literacy that would flow from education
prevents them from becoming empowered at any time in their lives (as cited in Health
Literacy, 2014).
A more informed view of health literacy includes the ability to understand
scientific concepts, content, and health research; skills in spoken, written, and online
communication; critical interpretation of mass media messages; navigating complex
systems of health care and governance; and knowledge and use of community capital and
resources, as well as using cultural and indigenous knowledge in health decision making
(Health Literacy, 2014).
This perspective defines health literacy as the wide range of skills, and
competencies that people develop over their lifetimes to seek out, comprehend, evaluate,
and use health information and concepts to make informed choices, reduce health risks,
and increase quality of life. While definitions vary in wording, they all fall within the
conceptual framework offered in this definition (Health Literacy, 2014).
Implications
It has often been said that knowledge is power, and information is the mother of
decision. People need information to make informed choices and decisions. The Bible

38
says that people are destroyed because they lack knowledge (Hos 4:6). The Nyagiki
church members need to be empowered with the correct HIV/AIDS information to help
them and the community around them. Through my project, Nyagiki church members
will be prepared to demythologize the society. My goal in this project is to ensure that
every church member has the basic information about HIV/AIDS and will be ready to
share that information with the people under his or her circle of influence and no person
should die from HIV/AIDS because he or she did not receive information on time.
Definition of HIV/AIDS
Human immunodeficiency virus infection and acquired immune deficiency
syndrome (HIV/AIDS) is a disease complex of the human immune system caused by
infection with human immunodeficiency virus (HIV). Following initial infection, a
person may experience a brief period of influenza-like illness. This is typically followed
by a prolonged period without symptoms. As the infection progresses, it interferes more
and more with the immune system, making the person much more vulnerable to common
infections like tuberculosis, as well as opportunistic infections and tumors that do not
usually affect people who have working immune systems. The late symptoms of the
infection are referred to as AIDS. This stage is often complicated by an infection of the
lung known as pneumocystis pneumonia, severe weight loss, a type of cancer known as
Karposi's sarcoma, or other AIDS-defining conditions (HIV/AIDS, 2014).
HIV is transmitted primarily via unprotected sexual intercourse (including anal
and oral sex), contaminated blood transfusions, clinical needles, and from mother to child
during pregnancy, delivery, or breastfeeding. HIV cannot be transmitted by saliva, tears,
vomit, feces, mosquitoes, or bedbugs (Holden, 2003, p. 4). Prevention of HIV infection,

39
primarily through safe sex and needle-exchange programs, is a key strategy to control the
spread of the disease. There is no cure or vaccine; however, antiretroviral treatment can
slow the course of the disease and may lead to a near-normal life expectancy. While
antiretroviral treatment reduces the risk of death and complications from the disease,
these medications are expensive and have side effects. Without treatment, the average
survival time after infection with HIV is estimated to be 9 to 11 years, depending on the
HIV subtype (HIV/AIDS, 2014).
Genetic research shows that HIV originated in West-central Africa during the late
19th or early 20th century. AIDS was first recognized by the United States Centers for
Disease Control and Prevention (CDC) in 1981 and its cause—HIV infection—was
identified in the early part of the decade. Since its discovery, AIDS has caused an
estimated 36 million deaths worldwide and approximately 35.3 million people are living
with HIV globally (as of 2012). HIV/AIDS is considered a pandemic—a disease outbreak
which is present over a large area and is actively spreading (HIV/AIDS, 2014).
According to Weinreich and Benn (2004), the most affected area worldwide is sub-
Saharan Africa where more than two-thirds (26.6 million) of all HIV-infected people live.
In the year 2003 in Africa alone 2.3 million people died of AIDS and 3.2 million people
were newly infected with HIV. The life expectancy in sub-Saharan Africa is 47 years;
without AIDS, it would be 62 (Weinreich & Benn, 2004, p. 8). Epstein (2007) calls this
situation “the African earthquake” (p. 67). Nolen (2007) argues that there were 28 million
people living with HIV/AIDS as of the year 2007 (p. 17).
HIV/AIDS has had a great impact on society, both as an illness and as a source of
discrimination. The disease also has significant economic repercussions. There are many

40
misconceptions about HIV/AIDS such as the belief that it can be transmitted by casual
non-sexual contact. The disease has also become subject to many disputes involving
religion. It has attracted international medical and political attention as well as large-scale
funding since it was identified in the 1980s (HIV/AIDS, 2014).
HIV/AIDS in Kenya: Statistical Information
According to Wikipedia, the HIV prevalence rate in Kenya is declining—which is
good news. This is has been made possible by two major factors: significant behavioral
change and increased access to ART (antiretroviral drugs). The National adult HIV
prevalence is estimated to have fallen from 10% in the late 1990s to about 6.1% in 2005.
Women generally face considerably higher risk of HIV infection than men and
experience a shorter life expectancy due to HIV/AIDS. “HIV/AIDS in Kenya,” (2014)
records an HIV prevalence rate of 8% in adult women and 4% in adult men. The Kenyan
people who are especially at risk include injecting drug users and people in prostitution,
whose prevalence rates are estimated at 53% and 27%, respectively. Men who have sex
with men (MSM)—the homosexuals—are also at risk at a prevalence of 18.2%. The list
includes discordant couples (where one partner is infected and the other is not), prison
communities, uniformed forces, and truck drivers.

41
Table 2
Overview of the HIV Epidemic in Kenya in 2013
• 101,560 Kenyans were infected with HIV
• 12,940 children, 50,530 women, and 38,090 men were infected with HIV
• 65% of new HIV infections occur in 9 out of 47 counties (Nyagiki Church
belongs to Kisii County where there were 5,975 new infections).
• 21% of new adult HIV infections occur among young women aged 15-24 every
year.
• 1.6 million adult Kenyans were living with HIV
• 191,840 children (below 18 years of age) were living with HIV
• 63% of men and 80% of women know their HIV status.
Source: (“HIV/AIDS in Kenya,” 2014).
------------------------------------------------------------------------------------------------------------
According to the Kenya National AIDS Strategic Plan (KNASP) 2005/6-
2009/10, about 65,000 Kenyan adults and 25000 children become infected with HIV
every year, while a total of 150,000 die of AIDS related disease annually (Wanjama et
al., 2013, pp. 13, 14). With the onset of HIV/AIDS, there has been quick increase of
other diseases (opportunistic infections) including tuberculosis, malaria, meningitis,
pneumonia, and typhoid (p. 72). Other complications caused by HIV/AIDS include
absenteeism and low performance among the employees (especially those in the health
sector), having internalized and genuine fear of contracting HIV from AIDS patients
and blood contact. The worst of all seems the influx of orphans (kids without parents).
There are approximately 11 million orphans in Africa and most of them live in Sub-
Saharan Africa (Wanjama et al., 2013, p. 72). Callen (2010) asserts that we should not
be overwhelmed by the numbers but be willing to change one life at a time. This is
exactly the strategy used by Horizon International (A Faith-Based Organization) that
has done a commendable job in establishing orphanages across several African

42
Countries (South Africa, Zimbabwe, Zambia, Kenya, and Uganda) (Callen, 2010, p.
29). D’Adesky (2004), concurs with Callen that we should not view HIV/AIDS patients
as just numbers but lives to be saved one at a time. Furthermore, D’Adesky challenges
the mainstream USA media not to ignore HIV/AIDS as a problem of Africa and Haiti.
Stating that we can move mountains if we pull together (D’Adesky, 2004, pp. 4, 6).
Kenya’s Response to HIV/AIDS:
Three Phases of Response
In describing the response of the government of Kenya to the HIV/AIDS
pandemic, two schools of thought were consulted. The first school of thought was
advanced by Valet Mukotsanjera and the second thought was advanced by Doroth
Rombo and Jane Njue. According to Mukotsanjera (2008) Kenya’s national response
consisted of three distinct phases, the first lasting from 1984 to 1991, the second from
1992 to 1997, and the third from 1998 to 2005 (Mukotsanjera, 2008, p. 87).
Conversely, Doroth Rombo and Jane Njue (2012), describe Kenya’s response in three
phases, each phase comprising about 10 years (a decade): 1983 to 1992; 1993 to 2002;
2003 to 2014. The latter school of thought seems to be more descriptive and accurate;
consequently, this school of thought has received more space in this project
manuscript.
The First Decade 1983-1992
The response of the government of Kenya to HIV/AIDS in the first decade was
slow. The first publicly declared case of HIV was in September 1984, a few cases had
been observed in 1983. Mukotsanjera (2008) gives a slightly different date—1985—as
the year when Kenya had the first declared case of HIV/AIDS (p. 87). In the first decade,

43
HIV was largely unrecognized among the Kenyan population. Rombo and Njue quoting
from Lorch (1993) cite four reasons why the government of Kenya was passive in the
first decade to deal with HIV/AIDS. The first reason given was that the government of
Kenya was making effort to remain in power against the democratic waves that were
sweeping across the world that led to the end of the cold war in 1989. Secondly, the
government feared that making public HIV/AIDS prevalence could scare away tourists
coming to Kenya from outside countries. Third, there was limited medical knowledge on
HIV/AIDS. Lastly, there were limited financial resources to engage in research and
intervention strategies to combat the spread and invest in HIV/AIDS education (Rombo
& Njue, 2012). According to Epstein (2007), the major factor that delayed the response
of the country to HIV/AIDS was the fact that Kenya’s democratic space was limited and
therefore no major decisions would be made or implemented without the permission and
endorsement of the higher authorities (p. 68).
Kenya was not the only country that exhibited passivity in the first decade of
HIV/AIDS. This situation prevailed in most of the countries of Africa. It is apparent that
the continent was going through denial stage (Gill, 2006, p. 55). Bindenagel-Sehovic,
Annamarie asserts that South Africa, which now has the greatest prevalence of
HIV/AIDS cases in Africa, between 1981 and 1998, acknowledged the problem but chose
to prioritize on the domestic transition to democracy over the threat of HIV/AIDS. South
Africa also had three phases of response to HIV/AIDS. Beginning low and become more
active culminating in the establishment of a strategic planning (Bindenagel-Sehovic,
2014, pp. 16, 17). However, the policies of former president Thabo Mbeki—successor of
Nelson Mandela—proved counter-productive. Mbeki was contending that AIDS was

44
caused by poverty and not HIV and therefore there was no need to allocate financial
resources for HIV/AIDS patients to receive antiretroviral (ARV) therapy (Kalipeni et al.,
2004, p. 5). Tragically, since there was no national HIV/AIDS state of emergency
declared, there was little financial resources allocated to address this issue (Marlink &
Kotin, 2004, p. 143). Gill asserts that HIV/AIDS was a blind spot for Nelson Mandela
and Thabo Mbeki (Gill, 2006, p. 73). Thabo Mbeki was accused of playing games on his
people while young people were drying up and falling just like beautiful cut flowers
falling from a vase (Iliffe, 2006, p. 146). It is sad to observe that Nelson Mandela—like
his counterpart Bill Clinton of United States of America—became aggressive in fighting
against HIV/AIDS after retiring from active politics (Behrman, 2004; Gill, 2006, p. 66).
According to Smart (2002), South Africa became serious in addressing the AIDS
epidemic in the third decade of its existence (in other words, 20 years were lost in dilly
dallying) (Smart, 2002, p. 194). In sum, it is safe to conclude that Kenya (like South
Africa) lacked visionary leaders to deal with HIV/AIDS disaster at its onset and it
became difficult to eradicate it in its advanced stages.
The Second Decade 1993-2002
In this decade, Kenya moved from one party autocratic rule to embrace multi-
party democracy. The government was under strict scrutiny from the opposition party.
There was more accountability and transparency. By 1992 it had become evident that
HIV/AIDS was related to sexually transmitted infections and in 1994, the National AIDS
and STD Control Program (NASCOP) was established. The focus of attention included
sexually transmitted infection (STI).

45
The Sexual Education Bill of 1996 proposed the teaching of sex education to all
secondary (high) school students. The bill failed. The proponents of the bill intended to
engage the youths (high school kids) in a healthy talk to lay bare facts about how
HIV/AIDS is related to sex and how to avoid “unsafe sex” that would lead to HIV/AIDS.
The opponents aggressively reasoned that there was no need to talk about “safe sex” and
“unsafe sex” to the youths because that could be tantamount to encouraging them to
engage in sexual relationships (the position of the opponents was that any type of sex for
unmarried persons was unsafe).
With policymakers and stakeholders (especially the churches) divided on whether to
teach sex education in schools, the opportunity was lost to bring to the forefront the
spread of HIV and AIDS and devise preventive programs. The impact of HIV
continued to be felt across the country. Indeed, it took just 3 years after the sex
education bill failed to pass for the government to declare HIV a national disaster.
(Rombo & Njue, 2012, p. 16)
The Third Decade and Beyond 2003-2014
In December 2002, the people of Kenya elected a new president, Mwai Kibaki,
who took over from Daniel Moi (Moi had stayed in power for 24 years). The constitution
was changed so that a president was now entitled to be in power for a maximum of two
terms (each term having 5 years). In 2003, president Kibaki with his newly elected 9th
parliament formed a new parliamentary group which took proactive steps in combating
HIV/AIDS. Some of the steps that were taken included: first, launching extensive public
education through government ministries. Second, availing government money for
research initiatives on HIV/AIDS. Third, subsidizing the cost of medicine for the
individuals who were already infected with AIDS. Furthermore, emphasis was placed on
the existing ABC model: A, stands for abstinence, this targeted the youth and encourages
them to be celibate until the time of their marriage. B stands for being faithful to one’s

46
sexual partner- this applied to those who were married as couples and those who were
cohabiting. C stands for condom use, directed at high-risk groups like commercial sex
workers and long-distance truck drivers (Rombo & Njue, 2012, p. 16). Some of the
church members in the churches where I served as a pastor for fear of promoting
promiscuity among the church members campaigned for members to go for Conduct not
Condoms. This intervention appeared justifiable but did not provide a solution to persons
already infected with HIV/AIDS, for example the situation where one marriage partner
was HIV/AIDS positive and the other was negative.
From the year 2003, government agencies and private individuals in Kenya did an
assessment of the impact caused by HIV/AIDS. It was discovered that the effects caused
by HIV infection were economic, social, and psychological. The findings were reported
both in qualitative and in quantitative research. In sum it was found out that the greatest
impact of HIV/AIDS was felt by the family unit. Children become the innocent victims
when one or both parents are diagnosed with HIV/AIDS. “Stigmatization, dropping out
of school, change of friends, increased workload, discrimination and social isolation
against orphans all increase the stress and trauma of parental death (Rombo & Njue,
2012, p. 17).
In the year 2006, the government of Kenya passed two bills into law: The Kenya
HIV and AIDS Prevention act and The Sexual Offenses Act. The latter addresses sexual
offenses including rape, incest, and other acts of sexual violence which may cause the
offender to transmit HIV/AIDS to the victim. The Prevention Act focuses on the sensitive
issue of secondary and tertiary transmission of HIV. The Prevention Act was aimed at
stopping a person who was HIV/AIDS positive from spreading the disease to his/her

47
sexual partner or anyone else. Such a person is mandated by law to report his/her status to
the sexual partner and to make effort not to transmit the disease to him/or her. If such a
person cannot report his/her status, then the medical practitioner has the protection of the
law to report the patient’s HIV/AIDS status to his/her sexual contacts. If such a person
acts contrary and transmits the disease to another person, then this is an offense which
should lead to prosecution. The offender is liable for a fine not exceeding five hundred
thousand Kenya shillings or imprisonment for a term not exceeding seven years or both a
fine and imprisonment (Rombo & Njue, 2012, p. 15).
Implications
The Sexual Offenses Act (of 2006) has been hailed as a major turning point in the
fight against HIV/AIDS not only in Kenya but also in sub-Saharan Africa. Where
disclosure is done voluntarily, a HIV/AIDS patient can lead a better quality of life
receiving support from family members. On the other hand, trying to seek justice in the
event of a crisis is counterproductive as regards building trust among family members,
“Criminalization might cost the family its stability. HIV is highly stigmatized and
therefore the HIV free partner might not stay committed to the relationship. The Act
would serve discordant couples where one is positive and the other is negative if it were
not for stigmatization and cultural gender expectations including economic gender divide
that lead to negative outcomes for women living with HIV (Rombo & Njue, 2012).
Another loophole with this law was the fact that not all people suffering with HIV/AIDS
are willing to go for voluntary (not mandatory) counseling and testing (and some people
may intentionally avoid going for VCT to dodge the law.

48
Initiatives to Prevent the Spread of HIV AIDS
Foreign Aid
Melissa Buehler (2011, p. 8) contends that since many countries in sub-Saharan
Africa have limited financial resources, it is necessary to depend on foreign aid to
Combat HIV/AIDS disease. Buhler showcases major international donors that have been
instrumental in supporting Africa financially (p. 8). Some of the donors that she mentions
include WHO, UNAIDS, and Global Fund. The resources provided by the international
bodies have been supplemented by those provided by philanthropic organizations. Over
the years, Africa has continued to receive aid but the cases of people getting infected has
been overwhelming. The need to get aid has been more than the resources available. This
situation has led to the donors becoming selective on who to receive aid. However, it has
not been easy to establish the criteria for picking some countries to receive donor aid and
leaving others out (both countries face the same crisis) (Buehler, 2011, p. 18).
Sue Holden (2003) contends that HIV/AIDS is a complex developmental issue
and all sectors of development must actively play a part in eradicating it. According to
Anderson and Patterson (2017), the big question is not how much money is given out to
PLWHA but how much training is given on how to use that money for PLWHA to be
self-dependent and self-sustaining. In other words, rather than give fish to donor-
recipients, it is better to train them how to fish. Donors can give loans to groups to
engage in enterprises such as goat farming, raising chicken, small scale farming,
processing food, and making crafts to sell to tourists.
Nana Poku contends that we cannot solve the aids crisis in Africa without solving
the debt crisis (the silent crisis). Solving the aids crisis requires huge sums of money and

49
yet many African countries are heavily indebted (Poku & Whiteside, 2004). “Any
effective engagement with HIV/AIDS in Africa must simultaneously engage with the
continent’s economic decline, if it is to be effective and sustainable” (Poku & Whiteside,
2004, p. 33). In 1996, the World Bank and IMF came up with a plan to cancel debts from
countries that they termed, “Heavily Indebted Poor Countries (HIPC).” Conditions were
laid down which were required to be fulfilled to qualify for debt cancellation. By
September 1998, only five countries in Africa had qualified for this debt relief packages
and this resulted in the industrialized countries getting compelled to review the conditions
for qualifying for debt cancellation (Poku & Whiteside, 2004, p. 43).
Church Involvement
In the year 2000, there were 390 million Christians in Africa. Campbell argues
that churches can be a positive force in the community to stop HIV/AIDS: This statement
is based on two factors: First, churches are often the most well established community
networks in AIDS vulnerable communities, and thus potentially have wide influence; and
second, that church teachings of love and care open up many potential spaces for an
increased positive role in supporting people living with HIV/AIDS (PLWHA) (Campbell,
Skovdal, & Gibbs, 2011, p. 1204). An inquiry done by Edwin Hernandez discovered that
church members have responded both positively and negatively to the people living with
HIV/AIDS. The church members have simultaneously promoted acceptance (based upon
its understanding of mercy) and rejection (based upon its understanding of holiness) of
the HIV/AIDS population (Hernandez, 2005, p. 101).
On the other hand, churches can cast a negative impact in the effort to combat
HIV/AIDS. The churches increase stigma against people living with HIV/AIDS when

50
they use any of the following approaches: First, selecting to read passages from the Bible
that portray women as sinners who need punishment. Second, compelling women to be
submissive to domineering husbands. Third, shutting the doors against those who are in
non-heterosexual relationships (Campbell et al., 2011, p. 1212). Fourth, labelling as
“unfaithful” those who use condoms:
More widely it has been suggested that, within church groups, condoms have come to
represent ‘a tool for unfaithful wives’ or for those who have premarital sex. The
Mozambican example highlights how mainstream messaging about condoms may
contradict the positions adopted by powerful churches, highlighting the need to
involve church leaders in discussions about the design of health campaigns.
(Campbell et al., 2011, p. 1211)
There was associated tendency for churches to speak more on HIV prevention,
and less on the challenges of living with HIV/AIDS and undergoing treatment, or of the
potential role of church members in supporting PLWHA. HIV prevention messages
preached in churches were often limited to abstinence and fidelity which sometimes
clashed with “mainstream” HIV prevention campaigns (Campbell et al., p.1211).
Condom usage is a big issue among some devout catholic believers. This is because the
Roman Catholic Church teaches against contraceptives as a way of family planning. Park,
Currier, Harris, and Slattery describe a situation where a devout lady—Sheila Browne—
of the Catholic Church did not believe in contraceptives. Her sexual activity with her
husband—who was HIV/AIDS positive—was always unprotected and she got HIV/AIDS
from him (Park et al., 2017, p. 138). According to Shorter and Onyancha (1998), there is
hope for the church in Africa bringing behavior change that will check the spread of
HIV/AIDS. The case in mind is the youths of the Baptist Church have taken the initiative
to pledge to be abstinent until the time of marriage. Their movement is named, “love
waits” and records show that it began in the USA, where half a million youths have

51
signed the pledge of abstinence. The movement has now spread to 76 countries including
Kenya and Uganda (Shorter & Onyancha, 1998, pp. 107-109). One positive extra
advantage of the “abstinence pledge” will be the reversal of teenage pregnancies which is
a big issue in many African Countries (Webb, 1997, pp. 116, 117).
Support and Care of People Infected and
Affected by AIDS
People living with HIV/AIDS (PLWHA) live in communities and mingle with
people who are negative. To effectively minister to both groups of people—the infected
and the affected—there should be resources and organizations in the community to be
used. These organizations are technically known as “community-based organizations”
(CBO’s) (Kalichman, 2005, p. 193). Kalichman (2005) further argues that while in the
community, the issue of HIV/AIDS should be addressed at both individual and group
levels (p. 195). In the following paragraphs, I will highlight on the role the church—as
part of community organization—can play in supporting PLWHA.
Church Involvement
Campbell asserts that many churches in Africa have made progress in moving
beyond preaching about “prevention sermons” to preaching about “supportive sermons.”
Churches are community-based organizations and are to transform their communities if
they make a commitment to do so. Campbell reports that in Malawi many churches in the
rural areas are involved in caring for the sick, sponsoring HIV/AIDS education programs
for the youth, and emphasizing the care of orphans as a religious responsibility (Campbell
et al., 2011, p. 1214). A study done in Ghana found out that church members are
motivated to care and support PLWHA when they heard their leader publicly speak about

52
HIV/AIDS (Campbell et al., 2011, p. 1214). A study done in Mozambique found that the
involvement of church groups in the provision of assistance to be limited to
psychological support and personal care, neglecting many of the material and financial
needs of those affected. The possible reason for this could be because church members
are poor, but could also be an indicator of resource-based stigma (namely the belief that
PLWHA do not deserve to receive material support or services) (Campbell et al., 2011,
p. 1214).
Another study done in Tanzania revealed that PLWHA, despite lacking material
and financial resources, can cope with the threat better when they were assured of support
from God. They received comfort in their ability to confide in God and have an open
relationship with God. In Namibia, PLWHA found religion to be an important framework
to make sense of their illness and to come to terms with it. “The self-blame resulting from
the church’s teachings even helped some to make sense of their status in a way that
increased their sense of control over their predicament. Almost all participants reported
that since being diagnosed with HIV/AIDS, religion had become very important to
them—giving them a sense of meaning and purpose to life” (Campbell et al., 2011,
p. 1214). A research done by Harold Koeing in the USA found out that 55% to 65% of
Americans say that religion is important to their life and 79% find greater happiness,
satisfaction with life (Koenig, 2011, pp. 13, 15).
Campbell et al., observe that many church members and church leaders in Africa
are evolving from the situation of silence and condemnation to a situation of being active
and open in dealing with HIV/AIDS. A study done in Kenya found out that many people
disclosed their HIV-positive status to church pastors. A similar study in the Republic of

53
Congo found out that women were free to disclose their HIV status to church leaders and
supporting their fellow women to disclose their status to others including their husbands.
For people to be free to disclose their status, the church must be understanding and
accepting and be ready to encourage the members to live positively (Campbell et al.,
2011, p. 1214).
In some areas where church beliefs have prevented church members to act, social
action was used to tackle HIV/AIDS. Campbell uses the example of Kenya where youths’
groups affiliated to the churches and religious schools have resisted the moral doctrines
of church leaders and actively engaged in HIV management and condom distribution-
helping to create important social spaces for the prevention of HIV. Campbell et al.,
assert that for churches in Africa to be in the forefront of combating HIV/AIDS, there is
need to develop new theologies that are based on love and compassion to the sick and
disadvantaged in society:
Such theologies could, for example, challenge stigma through emphasizing those
aspects of the Christian message that potentially advocate for the forgiveness of
sinners; the empowerment of women; a compassionate understanding of the impacts
of poverty and other social inequalities on behavior; and recognition of the inherent
dignity of all human beings. (Campbell et al., 2011, pp. 1204-1219)
Government Intervention
According to Dworkin Shari, the war against HIV/AIDS is gigantic and needs
more intervention than the one provided by the churches. Some cultural practices help in
the spread of HIV/AIDS. Some of these cultural practices are deep rooted and require
strong government policies to eradicate, and they include: inequalities in resource
distribution, widow inheritance, and child labor. Dworkin did her research in two places
in Kenya—Kendu Bay and Kakamega. In this research, it was discovered that women are

54
frequently stripped of their property and other assets or evicted from their homes when a
husband dies of HIV/AIDS or other causes. During the funeral, the in-laws (brothers-in-
law and sisters in-law) come and loot the home taking away everything: pots, pans,
furniture, clothes, and sewing machines. The woman is displaced and then migrates to the
market or to the beach of Lake Victoria where she will exchange sex for money to
survive. Some women enter the “sex for fish” trade. Furthermore, some of the women
who have young girls (minors) encourage their daughters to enter into prostitution in
order to support their mothers to earn a living (Dworkin et al., 2013, pp. 704-708). Park
(2017) contends that forcing young girls to enter prostitution at a young age causes them
trauma that remains on them as permanent scars. Park however recommends a person
who experiences such trauma to seek professional counseling in order to reduce the
effects of post-traumatic stress disorder (PTSD) (Park, 2017).
Taban Legget and Wilfreda Thurston contend that it is a ridiculous situation that
some women feel that marriage is “unbreakable.” For example, Christian women cite the
marriage vow, “till death does us part” as a strong motivation to remain in an abusive
relationship and if possible, to die inside it. Other Christian teachings such as forgiveness,
love, patience, perseverance, and endurance on trials and affliction are promoting for
women to stay rather than to leave. Women with Muslim origins feel that they stand at a
disadvantage because the Islamic courts are dominated by men (Leggett & Thurston,
2009, pp. 36-40). Kathleen Greider (2007) asserts that sacred texts should not be used to
discriminate against people who are vulnerable. Ezra Chitando (2007) concurs with
Greider that sacred texts such as Ephesians 5:22-24 (“wives be subject to your husbands,
as to the Lord. For the husband is the head of the wife as Christ is the head of the

55
church”) are often misused to perpetuate male dominance. Patriarchy is not only present
in Christianity but in all world religions (pp. 6, 7).
Some women are compelled to be inherited: widow inheritance (Where a woman
whose husband has died is expected to have sex and/or marry or have a long-term
relationship with a brother in-law or a male relative. This kind of arrangement does not
stop but increases the spread of HIV/AIDS. The solution to this evil situation is to
improve the women’s ownership of property and assets. In the year 2010, Kenya voted on
a new constitution and a national land policy both of which could create a vibrant new
policy environment in which to improve upon women’s property rights and reduce
HIV/AIDS risks: “Now is the time to translate these innovative programs and national
policy shifts into targeted research agendas within the HIV/ AIDS prevention science
base, and to disseminate the findings of such research” (Dworkin et al., 2013, pp. 710,
711).
Material Support for Orphans
Studies done in Western Kenya reveal that where material support is provided,
there is a positive outcome in dealing with HIV/AIDS. Some of the material things that
orphans need include bed linens, mosquito nets, clothes, shoes, school uniforms, In Sub-
Saharan Africa (SSA), a surviving parent, grandparent, aunt or uncle are the main
caregivers for orphans, while some exceptionally vulnerable children live in orphan-
headed households. Care in orphanages has been deemed expensive and cost ineffective
due to high child-to-staff ratios, lack of social bonding and life skills, and stigma.
Although care by biological relatives is preferred, families in high prevalence, low
resource communities have become overwhelmed by the numbers and needs of orphans,

56
and remaining HIV-infected parents or other caregivers may themselves die before the
orphan reaches adulthood (Hallfors, Cho, Mbai, Milimo, & Itindi, 2012, p. 1101).
In Sub-Saharan Africa (SSA) where most new cases and deaths occur, an
estimated 15 million orphans have lost one or both parents. Orphan youth are more likely
to face malnutrition, school drop-out, poor psychosocial well-being and earlier sexual
debut. Efforts in providing basic needs to ensure that these orphans are kept in school
should be encouraged.
In a randomized controlled trial of 328 primary schools in Western Kenya, Duflo and
colleagues found that providing student uniforms significantly decreased school
dropout and marriage for both boys and girls, and pregnancy for girls when compared
to providing teachers with comprehensive training to deliver the Kenyan HIV
curriculum. (Hallfors et al., 2012, p. 1102)
After one year of exposure, this survey showed promising findings: There was
increased disagreement with early sex, increased bonding with adults in the family, there
was reduction in school dropout, sexual debut, and decreased support for wife beating
(p. 1102).
Conclusion and Recommendations for Nyagiki
Seventh-day Adventist Church
HIV/AIDS is a gigantic and complex issue and to eradicate it from society needs
the combined effort of individuals, families, organizations (including the churches), the
government and the international community. Given the fact that my project will engage
Nyagiki Church to make positive contributions to eradicate HIV/AIDS, I would like to
recommend the following strategies that Nyagiki can use in her effort to do so. First,
Nyagiki must make sure that her members have correct information. People need correct
information to make informed choices. The members must understand the basic
information about HIV/AIDS.

57
Secondly, the members must act to stop showing stigma to the PLWHA. PLWHA
should be loved unconditionally and be treated with dignity and respect. The Bible says
that there is no condemnation to those who are in Christ Jesus (Rom 8:1). Jesus said, “For
God did not send his Son into the world to condemn the world, but to save the world
through him” (John 3:17). The church leaders must set up a good example for members
to follow.
Thirdly, the church members must be ready to share their financial and material
resources to PLWHA. They should not wait for them to die and then put flowers on their
graves. The responsibility of caring and supporting others does not end. Some of the
PLWHA leave orphans behind when they die. In some cases, children lose both parents
and become helpless and traumatized. The church has a responsibility to care and support
these orphans. Above all the church has responsibility to empower PLWHA with skills
and knowledge on how to fish for themselves.
Fourthly, the church must act as advocates for the weak and vulnerable. It has
been shown that children and women suffer a lot when father/husband figure is absent in
the family. In Kenya, customary laws do not permit daughters to inherit property from
their parents. This situation makes women to be vulnerable. The situation becomes worse
when they are married, and their husbands die. When this happens, some of them are
compelled to move away from home, and some are forced to be inherited (widow
inheritance). Nyagiki church members have a responsibility of advocating for the rights
of children and women. They should be fearless to speak against evils such as widow
inheritance, child prostitution, and child labor.

58
CHAPTER 4
A DESCRIPTION OF THE TRAINING PROGRAM
Introduction
This training will be conducted at the Nyagiki Seventh-day Adventist Church in
the South Kenya Conference. About thirty adult church members will be trained to
minister to people who are suffering from HIV/AIDS in the church and in the
surrounding community. This training program will involve people who are 18 years of
age and above and will last for a period of two years. To make the training effective and
efficient, there is a need to have great strategies. This paper has made conscientious effort
to use several strategies including andragogy, Ubuntu/Umundu, Maslow’s hierarchy of
needs, Jethro’s principles, and Jesus’ teaching model. The training process will be
conducted in six phases which include engagement phase, exploration phase, explanation
phase, elaboration/extension phase, evaluation/assessment phase, and the
graduation/commissioning phase.
The Training Strategies
Andragogy
Andragogy is method of teaching adults that was championed by Malcolm
Knowles who is considered to be the father of Andragogy in USA (Foley, 2004, p. 89).
Andragogy is derived from the two Greek words andras which means man or an adult,
and agogos, which means “leader of.” Andragogy is therefore defined as the art and

59
science of teaching adults. Andragogy is contrasted with pedagogy. Pedagogy is derived
from two Greek words paid which means “child” and agogos, which means “leader of.”
Pedagogy is the art and science of teaching children (Knowles & Associates, 1984, p. 5).
In pedagogy, the teachers speak, and the students listen. This method of teaching was
prevalent before the 20th century. From the middle of the 20th century, we see radical
changes taking place and this is attributed to Malcom Knowles (Conoway & Zorn-
Arnold, 2016, pp. 37-42). From that period onwards, there was a paradigm shift: the
learner—rather than the instructor—is central to the process of learning (Knowles &
Associates, 1984).
Conoway and Zorn-Arnold (2016) developed six pillars to describe andragogy.
The six points are summarized below:
Experience
Experience is the knowledge we acquire by exposure to real life situations. It is
practical learning as opposed to abstract learning. Experience is one of the most
important of the six principles posted by Malcolm Knowles (Conoway & Zorn-Arnold,
2016). It promotes diversity since no two people possess the same experience. Many
adults can recall their past experiences and to connect with their present learning. “adults
naturally acquire life experience that is used as a framework to interpret past behavior as
well as a guide to future decisions” (Conoway & Zorn-Arnold, 2016). Knowles agrees
with Conoway and Zorn-Arnold that adults are the richest resources for one another
(Knowles & Associates, 1984, p. 10)
Wilson and Hayes (2000) argue that there is a difference between “learning from
experience” and “experiential learning.” The former happens in everyday contexts as part

60
of day-to-day life. Experiential learning, on the other hand, is systemized learning,
“specialized discourse,” that is organized to incorporate the location, a particular way of
thinking, and a particular ideological position or set of values (Wilson & Hayes, 2000,
pp. 73-74). To understand and value the experiences of other people, it is important to
understand the location and environment in which they were shaped. People do not get
experiences in a vacuum. People are shaped by the particular environment where they are
brought up (Wilson & Hayes, 2000, pp. 76-78).
Self-Directness/Autonomy
Students become autonomous in what, when and how they learn. They set their
own learning goals and objectives, they lay their own strategies on how to fulfill their
learning goals, they set their own deadlines and evaluate the progress made in reaching
the outcomes (Conoway & Zorn-Arnold, 2016). Wilson and Haya assert that andragogy
is individualized learning. Students make their own learning plans and take responsibility
for the outcomes (Wilson & Hayes, 2000, p. 58). Nicholas Corder agrees that andragogy
is student-centered learning. The student takes greater personal charge over his or her
own learning (Corder, 2002, p. 43).The instructor acts as a facilitator, coach, or resource
person—not a lecturer (p. 55). According to Siplon and Novotny (2007), women need to
be equipped with autonomy in order to deal effectively with HIV/AIDS. Women need to
identify their needs, values, and concerns and then make choices and plans relative to the
available resources. Autonomy means “self-determination,” “self-reliance,” “self-
discovery,” and “self-direction.” In other words there is no room for imposing plans and
procedures on others (Siplon & Novotny, 2007, pp. 90, 91).
Distance learning is a common phenomenon in the modern world. Many students

61
are opting to doing distance learning (Bash, 2005, p. 149). Weigel (2002) argues that
doing online courses is not only cheaper but it is also convenient; students can save the
time and money of commuting and staying in educational institutions (Weigel, 2002,
p. 127). The trend for most students is to do online courses and then transfer the credit to
the colleges/universities where they are enrolled to receive their degrees (Howell,
Williams, & Lindsay, 2003, p. 2). Bash (2003) states that about 90% of students in the
United States have access to a computer (Bash, 2003, p. 47). The future of distance
learning will depend on the students’ ability to use computers and technology.
Need to Know
Conoway and Zorn-Arnold (2016) assert that it is appropriate to inform adult
students why they must do specific tasks. The students are well informed of the learning
objectives from the start. Their coaches explain to them the relevancy and the cost of the
learning objectives, “Adults need to know that the resources they are investing (time,
efforts, money) will be worth it in the end. So reinforcing that point throughout the
course is important” (Conoway & Zorn-Arnold, 2016). Knowles agrees with Conway; he
says that adults learn in order to be able to perform a task, solve a problem, or live in a
more satisfying way (Knowles & Associates, 1984, p. 11). The role of the coach in
andragogy is to empower the students to be in charge of their destiny; they direct the
passion and energy of the students and do not force or compel them which will make
them develop resistance (Conoway & Zorn-Arnold, 2016, pp. 1-6).
Readiness to Learn
Older adult learners tend to be readier and more prepared to engage in studies
than young adult learners. Some young adult learners enter college having little passion

62
to engage in studies. Furthermore, some of them take a long time to decide which course
of studies to take. Older adult learners, on the other hand, tend to be more ready to be
engaged in study and tend to take their studies more seriously knowing the benefits they
will get if they succeed in school (Davenport & Davenport, 1984, pp. 152-159).
Orientation to Learning
For adult students, the future is now. “Their orientation is learner centered (versus
teacher-centered) and problem centered (Conaway & Zorn-Arnold, 2015, pp. 37-42).
Adult learners tend to be all set to engage in learning and do not need their teachers to
remind them (Conaway & Zorn-Arnold, 2015). Adult learners tend to study for the
present; instead of subject-centered orientation that is future focused, adults embrace a
problem-centered orientation that makes them to apply what they learn in their current
lives. Adults live for the present and not for the future (Imel, 1989, pp. 1-4).
Intrinsic Motivation
Children go to school because they must. They are extrinsically motivated by the
forces of reward and punishment (Ozuah, 2005, pp. 83-87). Adults go to school because
they want to. Tice argues that adults return to school in order to enhance their quality of
life and that of their family (Tice, 1997, pp. 18-21). Justice, on the other hand, argues that
adults who are over 40 years old return to school more for personal growth and
development rather than enhancing their vocational status (Justice, 1997, pp. 28-33).
According to Conway and Zorn-Arnold, adults return to school to be role models for their
children; “the pride and accomplishment that adult students expect from fulfilling their
degree is what motivates them the most” (Conaway & Zorn-Arnold, 2015, pp. 37-42).

63
Ubuntu/Omundu
Ubuntu is the African counterpart of andragogy. Ubuntu is derived from the
southern African Nguni language family. The bantu-speaking people of Eastern Africa
use omundu as a transliteration of Ubuntu. The Swahili fashion is mtu (human) and utu
(humaneness). Swahili is spoken by over 110 million people in the eastern part of Africa
(King & Wang, 2007, p. 63). Ubuntu means humanness or fellow feelings, kindness, or
empathy. Nobel Laureate Desmond Tutu defines Ubuntu as the essence of being a
person. A person is regarded complete when in intimate relationship with other fellow
human beings. A person is not complete alone. We are made for interdependence (King
& Wang, 2007, p. 64). Ubuntu is a timeless social philosophy that transcends time and
boundaries. “It is an African worldview enshrined in the maxim, umuntu ngumuntu
ngabantu (I am what I am because of who we all are).” A person is a person through
other persons and the selfhood is achieved by how we treat others and on the basis of
what we do for others (King & Wang, 2007, p. 64). The Eastern Africa transliteration is
omundu nomundu wa bandu (an individual is an individual because of other individuals
in society) (Nafukho, Amutabi, & Otunga, 2005, p. 11). Bangura (2005) argues that
ubuntugogy and omundogogy transcends andragogy.
Ubuntogogy is the art and science of teaching and learning undergirded by humanity
towards others. . . . Ubuntology transcended pedagogy (the art and science of teaching
children), andragogy (the art and science of helping adults to learn), ergonagy (the art
and science of helping people to work), and heutagogy (the study of self-determined
learning). (Bangura, 2005, p. 13)
Ubuntuism is based on human teaching and learning of all people in society without
identifying them as children or adults (King & Wang, 2007, p. 65).
If every human being on earth practiced Ubuntu, we could not have wars, poverty,

64
or human suffering. The resources could be shared equitably. Nussbaum asserts that
Ubuntu is a philosophy that defines the essence and purpose of human existence. A
person is blessed so that he/she can bless others. People are willing and able to share not
only their pains, but also their joys (Nussbaum, 2003, p. 9).
It is because of Ubuntu that some people in Africa were inspired to rise and do
great things to benefit other fellow Africans. Nelson Mandela was in jail for 27 years for
trying to redeem his country from apartheid. Julius Nyerere lived a simple life to assist
his people in Tanzania to enjoy better lives; Kwame Nkrumah dreamed of Africa
becoming “United States of Africa”—helping people to have good political governance
for better economic life and peace in the continent. Jomo Kenyatta of Kenya started the
“harambee” (pulling together) spirit.
Steve Bantu Biko (1946-1977) of South Africa is a good example of Ubuntu
ideology (“Steve Biko,” 2016). He was an anti-apartheid activist who was bold enough to
lead university students’ movements among blacks and people of color to challenge the
evils of apartheid in South Africa. He was arrested and was transported naked to a prison
680 miles away. He died on arrival in September 1977. Biko’s middle name is Bantu. His
parents gave him this name because they were thinking about the African social
philosophy Ubuntu; “a person is a person by means of other people.” Biko’s greatest
contribution was in motivating black people to have an identity and to regard themselves
as beautiful. He was famous for his slogan “black is beautiful,” which he described as
meaning: “man, you are okay as you are, begin to look upon yourself as a human being”
(“Steve Biko,“ 2016).

65
Jethro and Andragogy
Ber (2008) argues that throughout the book of Exodus, there is evidence of
opposing powers of conflict and resolution (p. 147). Conflict is seen in the side of
Pharaoh and God, but God overcame the conflicts and allowed the exodus to take place.
The forces of chaos and conflict do not spare the family of Moses. His two sons were
almost murdered by God but Moses’ wife, Zipporah, intervened to save them (Exod
4:24-25) (Ber, 2008, p. 147). God’s presence is not readily visible in the book of Exodus
18 (p. 150). Moses seems to be battling things alone until his father in-law, Jethro, came
to meet Moses. It is remarkable that God would use a gentile to communicate his wishes
to his people. God is not a respecter of persons (Acts 10:34).
Jethro saves Moses from burnout. He confronts Moses with these words: “the way
you are doing things is not right” (Ber, 2008, p. 165). The words of the narrator is that
Moses’ plan would “wear him out” which can be translated from the Hebrew verb NBL
to mean “ to wear oneself out,” “to be foolish” (Ber, 2008, p. 165). Lockshin makes a
more radical translation by associating the verb that is employed with the verbal root BLL
“to be confused” (Lockshin, 1997). “So in Jethro’s rhetoric, Moses’ way of management
is presented as a tiresome job, exhausting, foolish, and crazy activity (Ber, 2008). Jethro
envisions that if the plan that he proposed to Moses would be followed, then success and
victory will be their reward (Ber, 2008). Ber asserts that there is a happy ending in the
book of Exodus 18. Peace and harmony are reached through willingness to retreat, to
listen, and respond with understanding (Ber, 2008, p. 169).
Abraham Maslow and Andragogy
Maslow’s hierarchy of needs is a theory in psychology proposed by Abraham

66
Maslow. Maslow fully expressed his theory in his 1954 book Motivation and Personality
(“Maslow’s Hierarchy of needs,” 2016). Maslow categorized the human needs into six
levels and put them into a pyramid beginning from the most important to the least
important:
Physiological Needs
Air, water, and food are survival needs for both animals and humans. Clothing
and shelter provide protection from the elements. Maslow listed sexual fulfillment as one
of the physiological needs (“Maslow’s Hierarchy of needs,” 2016). A good teacher
should always check to find out whether a learner has physiological needs to be
addressed before engaging him/her in the learning process.
Safety Needs
People have a need to feel safe. This includes the physical safety (absence of war,
child abuse, and family violence), financial safety (stable jobs and employment), health
and wellbeing.
Love and Belonging
This includes needs for friendship, intimacy, and family
Self-esteem
Human beings have a need for stable self-respect and self-esteem. Treat people
with love and respect.
Self-actualization
“What a man can be, he must be.” This refers to a person’s full potential and the

67
realization of that potential. For example one person’s potential is to become an ideal
parent, another person may desire to become the best athlete, while another person may
desire to become a painter (“Maslow’s Hierarchy of needs,” 2016). In later years of his
life, Maslow admitted that self-actualization is not enough. Human beings have a desire
to connect with the supernatural power and then to receive fulfillment by exhibiting the
qualities of peace and goodness (Koltko-Rivera, 2006, p. 304).
Self-transcendence
Maslow explored a further ultimate goal of all human beings: “a higher goal
outside oneself, in altruism and spirituality” (“Maslow’s Hierarchy of needs,” 2016).
Jesus the Master Teacher
David Parkins asserts that to be an effective teacher one needs more than content
knowledge. A great teacher must have the ability to effectively communicate and
effectively engage the students in the learning process (Perkins, 2007, p. 34). Many
educators see Jesus as a great teacher of all time. Maxwell (1992) calls him “the master
teacher” (p. 18). Francine Wasukundi (2012) gives about six strong factors that makes
Jesus stand out as a great teacher (p. 264).
1. He asked questions (Matt 17:25; Mark 3:4; Luke 10:26).
2. He tested the ability of the disciples to discern and to think (Mark 6: 34-44).
3. He attracted the attention of his disciples (Mark 4:9, 23).
4. He sent his followers out on mission trips: He sent Seventy-two disciples and
Twelve apostles consecutively to the field—some kind practical training or

68
attachment (Mark 3:3-19). When they came back, he asked them to give
reports of their mission trip.
5. He provided enough instructions (Matt 18:15-22).
6. He engaged his disciples in a dialogue (Matt 10:5; 19:16-29).
Edward Watke (1995) argues that Jesus was a competent teacher because he
involved his disciples in their own learning. Jesus used the outlook and information that
his students gave to discern the deeper longings of their hearts. Roger Bybee (1996)
describes the 5Es sequence for teaching and learning: Engage, Explore, Explain, Extend
(or elaborate), and Evaluate. The evaluation is both the students and the teachers to
determine how much learning and understanding has taken place (Bybee, 1996). David
Perkins (2007) emphasizes that evaluation and assessment should be an ongoing
diagnostic process that allows the teacher to determine if the learner has indeed learned
(p. 86).
William Robertson (2008) describes Jesus as the greatest constructivist of all time.
This is evidenced when we analyze the way Jesus related with his disciples. He
continually challenged them through the use of experiences, parables, and questions in
order to help them think for themselves and develop new concepts (p. 1). Jesus avoided
spoon feeding his followers and instead he allowed them to discover and analyze new
concepts. Robertson asserts that Jesus’ use of the parable of the sower is strong proof of
Jesus as a constructivist. Through this parable Jesus moves his disciples from the known
to the unknown (p. 1).
What is constructivism? Brooks and Brooks (1993) define constructivism as a
learning strategy that builds upon students’ existing knowledge, beliefs, and skills.

69
Students work to synthesize new understandings based on their current experiences and
their prior learning. According to Eisenkraft (2003), in constructivism, learners of all
ages build new ideas on top of their personal conceptual understandings. Students and
teachers experience work together in applying and building on prior knowledge, “learners
construct meaning while continually assessing their understanding of concepts”
(Eisenkraft, 2003, pp. 57-59). Duffy and Jonassen (1992) point out that each learner has
their own construction, their own understanding , rather than some common reality
(Duffy & Jonassen, 1992, p. 6). Hofstein and Yager (1982) argue that the facilitator
utilizes open ended questions in order to assess their understanding and to engage the
students in learning. Robertson (2008) asserts that Constructivism is a very important
method of teaching because it makes the learners to take responsibility in learning by
being involved in active strategies that require them to problem solve and think critically.
Students gain a deeper and broader knowledge that is both practical and functional in
their everyday lives.
Nyagiki Participant Training Process
The best way to build a house if one does not have lump some capital is to do so
in phases: First lay the foundation, then build the walls, then put up the roof, then put up
the doors and windows, then do the plastering, lastly do the painting. Building in phases
will make a person who does not have enough resources to feel less overwhelmed. The
training program at Nyagiki will be done in several phases and it is expected that the
participants will finish the training feeling strong and enthusiastic.

70
Engagement Phase
The Recruitment Process
Thirty participants will be recruited. The goal is to have a minimum of 20
participants but given the fact that some participants may opt to drop out of the training,
it will be prudent to begin with a bigger number to provide room for those who may drop
out. All participants must be at least 18 years old. The selection criteria of all participants
will be based on their willingness to be involved in the leadership training program.
Participating in this study is completely voluntary. There will be freedom to join in the
study and to withdraw from the study at any time without any penalty. Confidentiality
will be strictly observed.
An announcement will be made in the church bulletin and the first 30 people to
sign in will be selected. The announcement letter will outline the checklist of things
needed to make one qualify to enter the training. Each participant will be issued with a
handout having all the information of what to expect in the training. Each participant will
be required to sign a form of consent agreeing to participate in the training. Each
participant will also have a witness who will also countersign. The process of recruiting
participants will be done in a very friendly and transparent manner
Pretest
The participants will be given a chance to role play in visiting a HIV/AIDS
patient by the bedside. This activity is to assess the level of knowledge the participants
have in caring for a sick person. Participants will say how to care for this person in three
levels. Level one will be sharing the normal trends on how other people without training
will care for this person. Level two will be inviting few participants to care for the

71
person. Level three will be the researcher to care for the sick person.
Exploration Phase
Provides students with a common base of experiences “the learners’ identify and
develop concepts, processes, and skills based on open-ended approach in which students
actively explore their environment or manipulate materials (Robertson, 2008, pp. 5-8).
Spiritual Retreat
Participants will be invited for a one-day long retreat. The purpose of the spiritual
retreat is to give the participants a chance to connect with each other and to God.
Participants will get to know each other’s names their likes and dislikes. Participants will
be encouraged to divide into small groups of two or three for prayer purposes. Each
member will be encouraged to share personal needs and prayer requests to his/her prayer
partner.
As an ice breaker during the retreat, participants will be discussed about
Ubuntu/Omundu ideology. It will be emphasized that to show compassion to people who
are vulnerable is part and parcel of the African culture and philosophy. It will also be
emphasized that Heaven agrees with the Ubuntu ideology. Jesus Christ came to fulfill
Ubuntu and not to destroy it. Several passages will be used to show that Jesus is a God of
compassion and love.
Few passages will be used to show that Jesus is the personification of Ubuntu.
Jesus showed compassion to a leper (Mark 1:40-45); and to the woman caught in adultery
(John 8:1-11). The application that will be drawn from these illustrations is to remind the
participants that they have a responsibility to care for people who are suffering from
HIV/AIDS following the example set by Jesus. The retreat will conclude with the

72
formation of focus groups. Nyagiki Church is divided into four territories/Zones.
Participants will form four groups and each group will have a leader and a secretary and
will be assigned to one territory of the church. Special prayers of dedication will be
offered.
Explanation Phase
Students uncover the content surrounding the concepts they have been exploring;
“it gives teachers opportunity to introduce primary content materials such as formal
terms, definitions, and other content information” (Robertson, 2008, pp. 8-10).
General Information
Specific information will be given on how to care for people who are sick. I will
make effort to demonstrate the effective ways to care for the sick people and to visit some
people in the area who are sick. I will take four people to accompany me on the
demonstration tour. Members will discuss and build at least 30 verses (Each member to
come with at least one verse) that can be used to encourage people who are sick.
Members will also discuss relevant songs that can be used.
Book Reading Report
Each participant will be encouraged to read the book Ministry of Healing by Ellen
White. The purpose of reading this book is to develop the Christian foundations for
caring for people suffering from sickness. A chance will be given for the participants to
share the information gained among themselves and before the church members at the
camp meeting.

73
Health Information Literacy
on HIV/AIDS
Each member will be given essential information related to HIV/AIDS. Members
will be trained to differentiate between facts and myths. Handouts having relevant
information will be given to each member. The researcher will recommend books that
can be read to enlarge their knowledge. The purpose of this reading is to help participants
to be well informed so that they can give quality care to people suffering from
HIV/AIDS. It will also help them to be qualified to answer questions that may arise in the
process of providing care to these people.
Elaboration Phase
Elaboration phase is designed to extend the students’ conceptual understanding in
areas of skills and behaviors. Students are given opportunities to practice and refine their
skills and behaviors in authentic contexts to deepen and broaden their understanding both
inside and outside the classroom (Robertson, 2008, pp. 10-12).
Monthly Meetings and Reports
Each focus group will be meeting once in a month to plan ministry and to give
reports. The group leader will chair the meeting and the group secretary will record the
discussions. This will be a right forum for the members to share experiences of their
visitation program to receive support and encouragement from their fellow members.
Each group will be expected to give a written report of the number of people visited each
month. A form will be given to help each group give relevant information. The group
secretary will receive reports from their members and then forward it to the chief
secretary. The chief secretary will forward the reports to the researcher. The researcher

74
will evaluate the reports and give necessary feedback.
Visitation Program
The goal of the groups is to provide care for the people suffering with HIV/AIDS
who have self-declared their status. People having different diagnoses will also be visited.
All the members forming a group will not be required to visit each single case. The plan
will be having two people visit each single case, but the groups will be very flexible in
their approach. In some cases, only one person will be needed to visit. The patients will
be contacted to give their suggestions on how they would like to be visited. The strategy
is to reach out to all people in the community who are suffering from different kinds of
sicknesses. Instructions on the proper way of doing home visitations will be provided.
Lessons of proper listening and having a non-judgmental spirit will be emphasized.
Follow Up
Jesus healed a blind person by touching him twice (Mark 8:22-26). At the first
touch the person was not able to see clearly—he saw people moving as trees. The
person’s eyesight was completely restored at the second touch. The participants will have
a follow up plan on all people visited. At the end of each visit, participants will leave
their contacts address with the patients and make them aware that they are free to call if
they need more help. When patients are visited more than once, they feel valued and are
able develop deeper relationships.
Public Outreach Program
The participants will be prepared to share publicly the information learned. This
will be done in the month of August and will be a one-week activity (from Monday to

75
Saturday) at the annual camp meeting. The researcher will be the keynote speaker at this
camp-meeting. The participants will team up with the researcher to give a “health-talk”
which will last for a period of 30-40 minutes each day (Monday to Friday). The strategy
is to have each focus group have one day in a week to present. The content to be shared
will be the information gathered form the books and their personal experiences in home
visitations.
Evaluation/Assessment Phase
Students assess their own understanding and abilities and allow the teacher to
evaluate the students’ understanding of key concepts and skills development (Robertson,
2008, p. 12).
At the end of the one-year period, the overall assessment of this training program
will be conducted by the researcher to determine the impact of the training program on
the lives of the participants. There are three methods that will be employed in the
assessment process: (a) focus groups, (b) personal interviews and (c) reflection journals.
Focus Groups
There will be four groups comprising 5-6 members. Each focus group will meet
for about 90 minutes to discuss and answer seven questions. All the four groups will have
the same set of questions. These questions will be short, simple, and down to the earth.
The participants will have a chance to have the questions in advance to help reduce
anxiety and give them a chance to think about the answers to give. The group leaders will
lead in the discussions and the group secretaries will record the answers. Each group will
meet separately for deliberations and then will join to present their findings.

76
Personal Interviews
This method of assessment is appropriate to ensure there is maximum
contribution and feedback from each participant—in a relaxed setting without fear or
intimidation from fellow group members. A signing sheet will be provided for the
members to sign to make an appointment to meet with the researcher. Communication
will be given about the time, location, and the duration for each interview session. Each
interview will last between 20 and 30 minutes. The sessions will be recorded to store
information for future use. The participants will be duly appreciated and affirmed for
their willingness to participate in this exercise.
Reflective Journals
At the end of the one-year period, the participants will be asked to write a one-
page reflection paper describing their positive and negative experiences. Participants will
be requested to share major lessons learned and provide recommendations for future
trainings. The reflection papers will be submitted hard copy or by email.
Post-test
Students will be given a chance to role play on caring for a person suffering from
HIV/AIDS. The researcher will assess progress made by comparing it with the pretest.
Graduation/Commissioning Phase
The participants will be encouraged to participate in the graduation ceremony.
This event will mark the end of formal training of the participants. While the training
session will end, ministering to people who are sick will continue at Nyagiki Church.
Nyagiki Church members will be invited for this occasion. The reading will be made

77
from Matthew 25:31-46 (the sheep and the goats). Participants will be given a certificate
showing their names and special prayers will be offered. The purpose of this event will be
threefold. First, graduation event is intended to give special recognition to the participants
in receiving the training. The second purpose of the graduation ceremony is to motivate
and empower the participants to use the knowledge gained to serve others. The third
purpose of the graduation ceremony is eschatological in nature. The participants need to
be encouraged to look forward to the parousia (second coming of Jesus). Jesus has
promised to give special reward (eternal life) to people who are involved in relieving the
needs of their fellow men/women: “His master replied, well done, good and faithful
servant! You have been faithful with a few things; I will put you in charge of many
things. Come and share your master’s happiness!” (Matt 25:21).
Conclusion
A story is told of one person who was quickly walking home on a cold snowy
winter night. His body was slowly giving way to the cold and he doubted whether he was
going to make it home alive. And then he saw another man fallen by the wayside shaking
with cold. After spending a few seconds debating in his mind whether he should help him
or not, he finally decided to help. He used a lot of energy to pull him off the ground and
hold him in balance to walk forward. As the two men put their arms around each other’s
waist to support each other in the journey, they generated enough heat that made each of
them reach his home safely.
It is not a waste of time and money when we sacrifice our time and resources to
help people who are vulnerable. The blessings we receive are like a two-way traffic—
they flow to others and to ourselves. The researcher will make assertive effort to explain

78
the benefits of making use of the African Ubuntu/Umundu ideology in showing love and
compassion to people suffering from HIV/AIDS. The participants will be inspired in their
work by the example of the great master teacher who gave his life to save people from
eternal death. His life was completely consumed in ministering for others and as a result
he was exalted to heaven to sit on the throne with God. Angelo Amato says that a good
teacher is like a candle, it consumes itself to generate light for others (Amato, 2000, p.
282).

79
CHAPTER 5
NARRATIVE OF THE INTERVENTION
IMPLEMENTATION
Introduction
Chapter 5 provides a narrative of my project challenge. This is an implementation
of the plan and strategies discussed in chapter 4 and takes place in a period of 18 months.
To keep the motivation high for the participants over this extended period and to provide
quality training, adult-friendly approaches are used in communicating information and
implementing the objectives. These approaches are borrowed from four educators
namely: Malcolm Knowles, Jethro, Abraham Maslow, and Jesus Christ. The training
ends on a high note with the participants speaking at a camp meeting leading into a
graduation ceremony. The project of training Nyagiki church members to deal with the
threat of HIV/AIDS was successfully accomplished.
Development of the Training Strategies
Malcolm Knowles’ Andragogy Model
I made use of the andragogy method as championed by Malcolm Knowles. Under
this teaching method, I allowed the participants to share their experiences and to be self-
autonomous. I empowered the participants to be ready to discuss their perspectives and
not to allow other people to impose information on them. Much of the learning was
“distance learning” given the fact that I supervised the learning from United States of

80
America. I acted as a facilitator, coach, or resource person. The African translation of
Andragogy is “ubuntology” which means “I am because we are, and we are because I
am.” In the words of the apostle Paul, all human beings are a single body. When one part
of the body is sick and suffering, it affects the whole body (1 Cor 12:26). In application,
if one person is suffering from HIV/AIDS the whole body (all human beings) suffers and
should feel morally responsible to help the person that is suffering
Jethro’s Model
In keeping with Jethro’s advice to his son in-law—Moses—I endeavored to
engage the participants by allocating responsibility to them. The “Chain of command”
was practiced. The participants were grouped into four zones and each zone had a
chairperson and a secretary to help facilitate monthly meetings. The four zones were
representative of the four territories of the Nyagiki SDA Church. The group secretaries
shared information to the executive secretary who shared information to the researcher.
Abraham Maslow’s Hierarchy of Needs Model
According to Abraham Maslow, physiological needs such as air, water, food,
clothing, and shelter are both basic needs. This list followed by need for safety, need to
be loved and to belong, and need for self-respect and self-esteem. In the effort to care for
people living with HIV/AIDS, the participants were encouraged to be observant of the
needs of the people living with HIV/AIDS and to bring those needs to the church so that
the church would plan to assist those lacking basic needs such as food and shelter.
Jesus Christ’s Discipleship Model
I utilized some of the techniques that Jesus used in training his twelve apostles. I

81
began from the known to the unknown. I encouraged the participants to be critical
thinkers who were willing to reason from cause to effect. We discussed information
together, I demonstrated for them on how to do ministry and then I sent them out—in
groups of twos or more—to do ministry and then they reported back to me their
accomplishments. I closely supervised their work and appropriately provided feedback.
The Training Process
The process of training the participants may be compared to the work of cooking
ugali (corn meal). Ugali is a staple food in many parts of Kenya (and other countries in
the Eastern and Southern parts of Africa). The ingredients of ugali are simple (water and
corn flour) but it takes a lot of skills to cook a good ugali meal. The process includes,
having enough fire (most people use firewood), bringing water to the boiling point,
adding flour in two major stages, using energy to thoroughly smoothen the dough with a
cooking stick (pounding and turning the dough must be done repeatedly until the dough is
completely refined). Just as it takes time and effort to cook ugali, it took time and effort
to train the 24 participants. It will take the work of the Holy Spirit to be refined for
service. Just like the apostle Paul, I made three missionary journeys to Kenya to provide
training and to gather data. In reporting this training, three phases have been used
namely: Engagement/Exploration phase, Explanation/Elaboration phase, and
Evaluation/Assessment Phase.
Phase One: Engagement/Exploration—
March 23-April 3, 2016
The research participants were recruited, and the rules of the game were explained
in detail. The consent forms were signed, and the ball was set in motion. Tim Sensing

82
asserts that Qualitative research must be done in a qualitative way and must ensure that
the best practices are followed. Some of the best practice ingredients that were present in
my research include the following ingredients: informed consent, confidentiality and
anonymity, academic integrity, inclusive language, and continuous evaluation and
assessment (Sensing, 2011, pp. 34-38).
The Recruitment Process
On March 26, 2016, the church elder announced that those who wanted to
participate in the study were to remain behind after the sermon. Information such as the
minimum age, duration of study, visitation program and monthly meetings was shared.
After this, pieces of paper were given out for those who wished to join the training to sign
their names. It was announced that the first 30 participants to turn in their pieces of paper,
could be recruited. A total of 24 adult members signed up for the training (eighteen
women and six men) and all of them were recruited.
Consent to Participate
It was made abundantly clear that participation in the research project was free.
The members are free to join in the training and free to withdraw at any time without any
penalties. After reading through the Andrews University IRB (Institutional Review
Board) protocol describing the rules and expectations of the participants, the members
signed the consent forms (Sensing, 2011, p. 34). Furthermore, each participant was
required to have a witness to countersign his/her form.
Name of the Group
The participants unanimously voted to have their group named “Elisha.” The

83
reason why this name was chosen was because Elisha had been kind to Naaman who was
suffering from what was considered an incurable disease—leprosy— (2 Kgs 5). Elisha
played a simple role to have this miracle happen: He referred the person to go and wash
seven times at the river Jordan and he was cured. The participants were passionate to
provide a cure to people suffering from HIV/AIDS. They recognized that the role they
could play was to refer people to Jesus, “The great physician.”
Building Rapport
Participants were given a chance to familiarize themselves with each other. Each
team player was given approximately three minutes to introduce himself/herself:
mentioning the full name, home area, and any point of interest. I set an example and
allowed others to follow suit.
The Pretest
The participants were given a task to role play visiting a HIV/AIDS patient lying
in bed looking seriously sick. One the participants played a role of sick person lying in
bed pretending to be seriously sick and volunteers were asked to come in to minister to
his emotional and spiritual needs. The researcher observed as several participants played
the role of a “chaplain” in providing care.
The Participant’s Toolbox
It would be disastrous to send soldiers to war without giving them weapons. The
following are a set of spiritual resources that each participant was encouraged to possess.
Choosing these spiritual resources was informed by the fact that religion supports
healing. Many modern doctors believe that religion enhances health and should be

84
integrated into medicine (Chamberlain & Hall, 2000, p. 4). Some of the health blessings
that come when people practice good religion include: “longer life, less illness, better
physical and mental health, marital stability, less divorce, less suicide, less abuse of
alcohol and other harmful substances (Chamberlain & Hall, 2000, p. 80). “Religion is
Good Medicine” (Chamberlain & Hall, 2000, p. 17).
1. A copy of the Bible: It was encouraging to know that each participant had a
personal copy of the Bible. We took time to build a list of Bible texts that could be
suitable to be used in caring for people who are feeling unwell emotionally, physically
and spiritually. The major texts that were chosen include the following: 2 Kings 5; 2
Chronicles 7:14; Psalm 103: 1-3; John 8:1-11; John 10:10; James 5:13-18.
2. “Ministry of Healing” Book: The researcher provided each participant with a
copy of this book written by Ellen G. White. The purpose of giving this book was to
encourage the participants to get acquainted with Jesus’ Model of caring for sick people.
Jesus is fine example of the ministry of healing.
3. A copy of the song book (Adventist hymnal in ekegusii language). The
participants chose a theme song to guide their ministry. The song is entitled, “the great
physician is now here.”
4. General conference (of Seventh-day Adventist) documents on HIV/AIDS.
These documents were released by the health and temperance department at the general
conference session in Indianapolis, Indiana, 1990 (Health & Temperance, 1990, pp. 93-
94, 109-113). They were very helpful in my project especially in preparing the
participants to speak at the camp meeting because of their brevity and simplicity. Since
85
these documents address HIV/AIDS from the Adventist Church perspective, they were
very relevant to the camp-meeting audience.
5. Textbook on HIV/AIDS. A book that gives information about prevalence of
HIV/AIDS in the country of Kenya. The book is entitled, HIV AND AIDS: The
Pandemic. It was written by Leah Wanjama, Elishiba Kimani, and Mildred Lodiaga and
was published by The Jomo Kenyatta Foundation (JKF) (2013, pp. 1-128). Four books
were given out to be shared among the participants (One book for each focus group).
Table 3
The Four Focus Groups (Zones) and Number of Participants
Zone
A
B
C
D
Total
No of
Participants
6
6
6
6
24
Source: Compiled by the researcher, Job Getange, March 2016.
Table 3 shows that four focus groups were formed with each group comprising of
six members.
Communication Protocol
Each zone had a leader and a secretary. I commissioned each group to visit
members in their zone. Each group met once in a month and gave a report of their
ministry in the community. Members agreed to meet on the last Sabbath of each month
for deliberations and to submit their visitation report. The group leader was then
obligated to submit the report to the executive secretary who was charged with the

86
responsibility of emailing the report to the researcher (Sensing, 2011, p. 130).
Community Outreach
To show an example on how to do ministry in the community, I led the entire
group to visit one lady in the community who had been sick and admitted in the hospital.
At the time we visited, this lady had been discharged from the hospital and was at home
undergoing recovery. She and her family had sent an invitation for us to visit. On
arriving, we sung several songs and I read words of encouragement from the Bible. After
that I prayed committing her into the hands of God.
Following Jesus’ example, a small group (inner circle) was formed, consisting of
the three elders in the group and we visited two families in the community. One family
had lost their son several months earlier and another family had a member who had
declared his HIV/AIDS status and he invited us to visit him.
Inauguration Ceremony
The research project was officially launched on Saturday 04/02/2016. The
program ran from morning till 4:30 p.m. in the afternoon and included Sabbath school,
sermon presentation, Holy communion, potluck lunch, and the music concert. Before the
sermon, the participants were invited to come forward and a prayer of dedication was
offered by the conference representative who was in attendance. I presented the sermon
from John 8: 1-11 which was entitled, “Neither do I condemn you, go and sin no more.”
After the sermon, the church members were invited to participate in the Holy
Communion which included foot washing, the unfermented wine, and the emblem of
bread. The congregation broke for a potluck lunch after which a music concert by the
church choir was held at the park—outside the church building. The church choir

87
members wore green clothes to match the green vegetation outside. The benediction was
offered, and the congregation was dismissed.
Spiritual Retreat
The original plan was to take the participants to a spiritual retreat about five miles
from their church to spend time for spiritual relaxation and refreshments. After
deliberations with the participants, a consensus was reached for them to have an
inauguration ceremony at their church which included Holy Communion. This was
conducted on April 2, 2016 and is outlined above.
Phase Two: Explanation/Elaboration—April 04,
2016-March 31, 2017
The Issue of Funding Explained
After several months of visiting the HIV/AIDS patients, the participants reported
to me that the needs were overwhelming. Some of the people living with HIV/AIDS
expected to receive financial support to help them meet some of their basic needs such as
food and money to buy drugs. This arose from the fact that the researcher resides in
America, which is regarded as a rich country by many Kenyans.
This experience is like what Peter and John went through when they met a beggar
at the entrance to the temple (Acts 3:1-10) who was expecting to receive money from
them. Peter and John were honest in their response, “silver or gold have we none, but in
the name of Jesus arise and walk. The participants were encouraged to be honest in
interacting with the vulnerable people and never to give false promises. In the consent
forms that the participants signed, it was clearly stipulated that no monetary payments
could be made either to the participants or to the care-recipients.

88
Case Study: Joe Muriuki
A “Case study” is the situation where the researcher uses another person or
church as an example of the ideal illustration that can be imitated or copied by others. “A
case study allows the researcher and participants to examine the lived experiences of
others” (Sensing, 2011, p. 141).
Joe Muriuki declared, “I have lived a full life despite being HIV positive”
(Muriuki, 2014). Muriuki is a Kenyan citizen who was diagnosed with HIV aids in 1987.
At that time, Muriuki had visited a small clinic to receive medical help after experiencing
minor ailments. After testing his blood sample, the doctor threw a bombshell at him,
“Muriuki, you could be HIV positive, and you are the first victim I have come across
with the virus” (Muriuki, 2014). Muriuki went for advanced examinations in two other
hospitals in Nairobi and the results were the same, he was HIV positive. Muriuki was
devastated by this news but the worst was yet to be revealed. Muriuki was told that he
had only, three months to live and he was advised to tell his wife to abort her three-week
old pregnancy. Furthermore, Muriuki was fired from his place of work and would not get
another job. According to Muriuki, this was a very traumatizing experience because at
that time, HIV was only associated with homosexuals and people of loose morals
(Muriuki, 2014).
Muriuki was the first person in Kenya to publicly declare his HIV status. Muriuki
decided to move from the capital city—Nairobi—and go back to his ancestral home—
Nyeri—to die. The good news is that Muriuki never died after three months. His wife
was HIV negative and gave birth to a baby boy who was also HIV negative. His wife was
like an oasis in the desert, she disregarded the calls from her blood relatives urging her to

89
pull out of her marriage to protect herself from getting infected with HIV by her husband.
On the other side of the coin, Muriuki continued to meet rejection and stigma because of
his HIV status. He could not get a job in his own hometown, he could not even open a
bank account. The stigma that he received did not end quickly. In 2006, Muriuki got a
visa to travel to USA but his visa was stamped, “HIV” status and he was advised never to
have sex with anyone while in the USA and never to go beyond the time granted in the
visa.
It is inspiring to know that Muriuki beat all obstacles to reach where he is today.
As of November 2014, Muriuki was a PhD candidate having teaching assignments in
three universities in Kenya. His son—the one he was advised to abort—was headed to
Malaysia to do a master’s degree in Technology. Muriuki founded “Know Aids Society”
to educate the whole country about the condition of HIV/AIDS. At the time of this
writing, Muriuki is almost 60 years and he hopes to graduate with a PhD in May 2015
(Muriuki, 2014).
There are five important lessons to learn from Muriuki’s story. First, it is
important for all persons to go for regular VCT to know their HIV/AIDS status. Second,
it is important for people to share VCT findings with members of their family, especially
their spouses. Third, it is important for those who test positive on HIV/AIDS to practice
high standards of self-discipline to self-care and to avoid spreading the virus to their
spouses and other people under the sphere of their influence. Fourth, it is important for
PLWHA to engage in productive activities to bless themselves and to bless others. Fifth,
it is important for PLWHA to shun all kinds of negative distractions and move forward to
achieve their personal and professional goals.
90
Monthly Meetings/Reports
The participants met in their focus groups once in a month. The meetings took
place at 2 p.m. on the last Saturday of the month. The agenda of such meetings was to
review the work done in visiting members in that month and to prepare a written report to
be submitted to the executive secretary. The group then planned the work for the
following month. The participants were encouraged to prepare to provide solutions to any
challenges that they faced along the way.
Home Visitation Program:
Table 4
Participants’ General and Special Visits at Nyagiki (April 2016- March 2017)
zone A
zone B
zone C
zone D
Total
Date of
Report
GV
SV
GV
SV
GV
SV
GV
SV
GV
SV
04/30/2016
4
0
3
3
5
2
10
0
22
5
05/30/2016
8
0
3
1
9
1
7
1
27
3
06/30/2016
8
0
5
4
7
2
8
0
28
6
07/30/2016
8
0
11
2
18
3
7
0
44
5
08/30/2016
3
0
8
4
3
0
4
0
18
4
09/30/2016
4
0
16
8
10
0
5
0
35
8
10/30/2016
5
0
2
2
7
1
7
0
21
3
11/30/2016
5
0
8
4
8
0
3
0
24
4
3/30/2017
4
0
2
2
10
0
11
0
27
2
Total
49
0
58
30
77
9
62
1
246
40
Source: Compiled by the researcher, Job Getange, April 2017.
Key: GV stands for General visits: Number of general visits made in each period.
SV stands for special visits made to people who have self-declared their HIV/AIDS status.

91
Table 3 shows the visits made by the participants to the Church’s four zones in a
period of nine months. It is good to understand that this is a compilation of the report of
the participants visiting people in the community whether the participants visited alone or
whether they visited in groups of two or more. Another point worthy of clarification is
that a visit to a home where there are more than one person in attendance is considered a
single visit when the people were met in a group under one session.
As shown in the graph, in a period of nine months, Zone A participants made 49
general visits and 0 visits to HIV/AIDS patients. Zone B made 58 general visits and 30
visits to HIV/AIDS patients. Zone C made 77 general visits and nine visits to HIV/AIDS
patients. Zone D made 62 general visits and one visit to HIV/AIDS patient. The total
general visits made by all the four zones were 246. The total visits made in nine months
to HIV/AIDS patients were 40.
Remarkable Monthly Experiences
In May 28, 2016, a member of group D, (EN) reported an experience of visiting a
married couple who were having a dispute. The wife was laying the blame on her
husband for not revealing to her that he was HIV/AIDS positive at the time they got
married and infecting her with the virus. EN listened to the grievances from both sides
and he advised them to attend VCT at the hospital. The couple accepted to do so. EN
helped the couple to understand that failure to have protected sex would lead to increase
of viral load and hence making the situation worse. He advised the couple to focus on the
present and not on the past.
On June 26, 2016, Group D visited a couple living with HIV/AIDS who had
refused to go for treatment claiming that they “are saved” and God will take care of them.

92
Group D helped this couple to understand that God is the one who gives the gift of
healing to the church (1 Cor 12). Jesus spent much of his time when he was on earth
healing people of their sickness. In John 10: 10 Jesus asserts, “I came that they may have
life and have it to the full.” After this visit, the couple were convinced that it is God’s will
for people to visit hospitals in order to get help.
On July 31, 2016, Group A reported that two people revealed their HIV/AIDS
status and they were encouraged to go for VCT. Group A also reported that they visited
five non-believers who decided to come to the church and become members through
baptism.
On October 04, 2016, group B reported that they had visited people having non-
HIV/AIDS sicknesses: two people with back pains and seven people with cirrhosis (liver
disease). While the focus was on HIV/AIDS patients, the participants went on a second
mile to bless other people in need.
On November 06, 2016, Group B reported that they visited a person suffering
from Asthma and they encouraged him to go to the hospital to seek help. They also
reported that they visited a couple that was HIV/AIDS positive who had stopped taking
their drugs. This couple was advised to go to the hospital for re-examination.
On December 4, 2016, Group D reported a critical situation of meeting a person
who had suffered from cancer for eight years. The person had serious wounds with a deep
hole. This person reported to the group that he visits local clinics as an outpatient. This
happened because he lacked enough funds to go to a bigger hospital. The participants
reported this matter to the church and arrangements were made to assist this person
financially.

93
Personal and Group Interviews
Personal phone interviews were conducted. Each participant was assigned a
maximum of three minutes. The phone interview was held on Saturday morning, January
14, 2017, and the participants were able to share their experiences and how they liked the
home visitation program and the challenges they faced. The event took place in the
middle of the project and was aimed at providing motivation and encouragement to the
participants.
Participants Visit the Researcher
All the participants visited me in my home on February 10, 2017. This was during
the funeral and burial of my father who had died on January 24, 2017. The visit of the
participants to my home met two important achievements: first it sends a strong message
that the researcher is also vulnerable (“a wounded healer”). The second achievement was
for me to make an evaluation of the effectiveness of the participants to minister to
individual members and to big congregations.
The participants were accompanied by their pastor and a few other church
members, a total of about fifty people. They gathered in my house around 10 am in the
morning after having travelled in a bus for about thirty miles. They stayed in my house
for about one hour and then they moved outside for a public funeral assembly. The
activities in the funeral program included short speeches, sermonettes, and songs. The
choir composed of the participants and other church members sung two songs. It was a
comforting experience for me and my family.

94
Phase Three: Evaluation/Assessment: April 1-
August 5, 2017
Reflective Journals
I originally planned that each individual participant was going to write one-page
reflective journal to share their experiences of the training. After deliberations with the
participants, it was agreed for the participants to provide feedback at the focus group
sessions—they agreed to do this assignment collectively rather than individually. The
focus group sessions were held, and the outcome is reported in chapter 6.
Post Test
The participants were given a chance to role play on caring for an HIV/AIDS
patient lying in bed feeling serious. One person laid in bed and several volunteers took
turns in providing spiritual care to this patient. The researcher carefully watched this
activity and compared it with the pre-test. The participants were given a chance to discuss
this activity to provide feedback. The critical analyses from the researcher indicated there
was remarkable improvement when compared to the pretest. The participants expressed a
lot of positivity and courage in providing care.
Camp Meeting Program
The participants and the researcher had the chance of speaking at the camp-
meeting. Every year a group of seven churches and two companies meet for a spiritual
refresher which begins at 9 a.m. and ends at 5 p.m. People commute daily to attend an
open air gathering for six days (Monday through Saturday). The trees provide shelter
from the sun and a good public address system is used in addressing the attendants. Each
of the four focus groups was assigned to give a health talk for 20 minutes each day. The

95
researcher was assigned to present the main sermon each day lasting for 45 minutes. The
participants were prepared to communicate information in a culturally sensitive way. Pike
(1993) asserts that we always need to be aware of the cultural differences when sharing
information across cultures. People may ignore good information if they feel that their
cultural perspectives have not been respected. For example not all Native Americans will
look one directly in the eye (Pike, 1993, pp. 299-301). In my own cultural setting, youths
will not feel comfortable to discuss the topic of sex with their parents of the opposite sex.
Saturday, July 29, 2017
We spent this day doing rehearsals for the camp-meeting. The Nyagiki church
members were gathered at their church and the researcher presented a sermon entitled
“The Transformation of the Ethiopian Eunuch” (He came to Jerusalem as a person, but he
went to his home as a Christian). This was because of the work of the Holy Spirit. The
members were encouraged to pray for the Holy Spirit to lead and cause transformation in
people’s lives. After lunch break, the participants met separately to draft the schedule for
camp meeting (topics and dates to present). The participants met in their focus groups to
choose two people to represent them. The researcher was available for those who needed
to connect on individual basis.
Monday, July 31, 2017
Two participants from zone A gave the health talk: they gave the definition of
HIV/AIDS, the symptoms, and the Seventh-day Adventist Church response (Health &
Temperance, 1990, pp. 109, 110). The sermon was based on Genesis 39:12 and was
entitled “Run out and save your life.” Joseph ran away and saved himself from
committing adultery with Potiphar’s wife. We need to run away from sin especially from

96
the sin of adultery.
Tuesday, August 1, 2017
Two participants from zone B gave the health talk focusing on how HIV/AIDS
viruses are transmitted, the treatment, and the global impact of AIDS (Health &
Temperance, 1990, pp. 110, 111). The sermon was entitled: “Be a good keeper of your
brother and your sister” based on the book of Judges 19:22-30. A foolish man slept while
his wife was raped all night, and, in the morning, she died. This was a moving story
helping couples to defend each other and not to engage in lifestyles that will put their
spouses at risk.
Wednesday, August 2, 2017
Two participants from zone C presented the health talk. They encouraged the
listeners to be proactive in sending the warning against HIV/AIDS everywhere, including
schools, churches, and homes (Health & Temperance, 1990, pp. 111, 113). The sermon
was based on the book of Hosea chapter 3 and was entitled “Grace brings a sinner home.”
Hosea’s wife was a prostitute who left home and went to live with her lovers. However,
Hosea used his resources to buy her back and bring her home. God’s loves sinners and he
gave his son to redeem them back. Where sin increased, grace increase much more.
When we show love to other people, we exhibit the character of God. (The conference
president attended the camp meeting on this day to provide support and encouragement to
the researcher and the participants).

97
Thursday August 03, 2017
Two participants from zone D presented the health message entitled, “Mobilizing
pastors, teachers, parents, church members, communities to be engaged in providing
information to help people avoid getting infected with HIV/AIDS.” Information was
given to help people learn how to exercise fidelity before and after marriage (Health &
Temperance, 1990, pp. 93, 94). The sermon was based on the book of Luke 23:26-43 and
was entitled “The cross: the place to receive forgiveness.” Just as God has forgiven us of
our sins, we also need to be ready to forgive those who sin against us.
Friday, August 4, 2017
The participants attended their graduation and received their certificates. The
sermon was based on the book of 1 Peter 1:7 and was entitled “Cast your burdens upon
him.” Sermon was an encouragement to pray; to be free to talk with God just the way we
are open to talk with our intimate friends.
Saturday, August 5, 2017
The sermon was based on 2 Samuel 9:13 and was entitled, “A lame man at the
King’s palace.” The sermon was an expository sermon describing King David showing
generosity to Jonathan’s son, Mephibosheth, who was lame. Mephibosheth was Saul’s
grandson (Saul was an enemy to David). Because of Jesus sacrifice at the cross, God is
going to allow human beings (who have been made lame by sin) to live in his heavenly
palace for all eternity. Just as God is kind and patient with us, we need to be kind to each
other (Avoid a non-judgmental attitude). After preaching this sermon, I made an alter call
and 29 people responded to the call.
98
Table 5
Nyansongo Camp-Meeting Attendants (July 31-August 05, 2017)
Day
Mon
Tue
Wed
Thurs
Fri
Sat
Attendance
72
161
364
535
432
1125
Source: Retrieved from Nyansongo camp-meeting secretary’s records, August 2017.
Table 5 shows the daily attendance of people at the camp meeting. It was
compiled at about 11 pm each day—just before the health talk and the sermon. It does not
reflect the attendance at the camp meeting throughout each day. Whereas there are people
who attended full time (morning till evening), other people opted to attend only part time.
The participants who spoke at the camp-meeting expressed a lot of knowledge,
enthusiasm and courage. An example is a lady who spoke in the presence of her father-in
law on the sensitive topic of using condoms as a weapon to prevent HIV/AIDS (among
the Kisii people, usually ladies tend not to address sensitive topics in the presence of their
parents’ in-laws). Such a courage is like the ones the disciples of Jesus demonstrated—
after His ascension—and it was said that “they turned the world upside down.”
Graduation/Commissioning
The participants had a chance to attend the graduation ceremony which was held
on Friday, August 4, 2017 at the camp site. It was very inspiring that all the 24
participants recruited lined up to receive their certificates which were given in a public
setting. The participants wore special uniforms (white tops and black bottoms) and were
invited to parade at the stage. The researcher read from Matthew 25:31-46 (the sheep and

99
the goats). The area pastor made some remarks encouraging the participants to be faithful
in the calling that they had received from God. He motivated them to look forward to the
second coming of Christ where they will be rewarded for the good work that they will do.
Each participant was given a certificate bearing his/her name, the course of study,
the period of training, and the name of the researcher. The certificates were signed by
three people: the researcher, the church pastor, and the church elder. A special prayer of
dedication was given by the area pastor.

100
CHAPTER 6
EVALUATION AND LEARNINGS
Project Summary
The Doctor of Ministry Research Project was conducted at Nyagiki Seventh-day
Adventist Church between March 2016 and August 2017. There were 24 adult
participants—18 women and six men—who were effectively trained on how to care for
people living with HIV/AIDS in their communities. The 24 adults were first equipped on
relevant basic information about HIV/AIDS. Special lessons were given on how to make
home visitations and how to share information in a friendly atmosphere.
The participants formed four focus groups and each group was assigned an area—
zone—to cover. The focus groups met once each month to give their progress reports in
reaching out to their communities. At the end of their training, the participants were
involved in speaking at a one-week camp meeting which was held in their community.
Two participants spoke at this event each day to represent each of the four focus groups.
The climax of the training was the issuing of certificates to the participants which was
conducted on Friday of the camp meeting week. The graduates were commissioned to
continue doing the ministry of caring for HIV/AIDS patients in their communities. Other
highlights in this chapter include: recommendations to Nyagiki Seventh-day Adventist
Church, my transformation as a ministry professional, and the conclusion.

101
Evaluation Method: Focus Groups
Questions Answered
There were six focus questions that were discussed by the participants. The
questions were the same for all groups, but the answers given were different. The focus
groups discussed the questions and they were encouraged to give at least one salient
answer to each question. The response is outlined below. I have endeavored to copy
directly the responses given (responses were written and submitted to me by the group
secretaries).
1. What positive experiences can you share for participating in the HIV/AIDS training
program?
Group A: “People can live longer and better so long as they accept their status and
know that God is the giver of life.” Group B: “With sweet words and encouragement . . .
indicated to us that making friendship with them can make HIV/AIDS patients to live
longer than expected.” Group C: “HIV/AIDS patients appreciated our visits and enjoyed
hearing the word of God and our prayers.” Group D: “We as a group, discovered that we
can live longer and better years if we know our status.”
2. What areas were not very helpful to you?
Group A: “Some of these patients expected material or financial support. Group
B: “Moving to individuals directly was not helpful because many don’t want to expose
themselves.” Group C: “Some patients we visited needed healthy foods to keep them
strong. It was unfortunate that we did not have any food to offer to them.” Group D: “The
method of knowing our fellows who are affected with HIV/AIDS (Identification).”
3. What areas would you recommend changed if we were to start all over again?
Group A: “If we could have a kit from where the sick is given at least something.”

102
Group B: “Avoid direct approach to the affected because those with stigma tend to
despise themselves.” “Improvise a method to create awareness through churches and
funeral meetings.” Group C: “The HIV/AIDS patients take strong drugs which tend to
weaken them. We should make effort to support them to have food security.” Group D:
“When visiting the sick people, we need to avoid discrimination and separation.”
4. How did this training change your attitude to people living with HIV/AIDS?
Group A: “This study helped me to see that HIV/AIDS patients have chances of
living longer and normal lives.” Group B: “The training helped me to understand how
HIV/AIDS patients feel and respond to stigma. It also helped me to know how to care for
them while maintaining confidentiality.” Group C: “HIV/AIDS causes a lot of suffering
to the people who are infected. We need to be faithful to each other within marriage and
to pray to God always so that he may protect us from getting infected.” Group D:
“People who are infected with HIV/AIDS are able to lead normal lives and can enjoy
activities such as singing, reading God’s word, and eating together to create love.”
5. How beneficial were the outreach programs?
Group A: “It made some patients like reading the Bible because we told them that
it was the source of life.” Group B: “It was a blessing to us and the people who received
the message. You can’t give what you don’t have, we shared out what we had first
gained.’ Group C: “This program helped me to study more about the word of God.”
Group D: “The outreach program helped the care-recipients to receive encouragement
and hope.”
6. How do you think this training program made you a better leader and Christian?
Group A: “It made me to be tolerant and know that this life has challenges and

103
without the word of God, one can lose hope in life.” Group B: The training helped us to
get detailed information and this made us to become role models to other members in the
church.” Group C: “This training helped me to know how to approach, comfort, and care
for people who are living with HIV/AIDS. It also helped me learn how to take good care
of my fellow Christians.” Group D: “This training was a motivation to read more books
and become better equipped to walk the Christian journey.”
Intervention Outcome
The monthly reports indicated that there was a total of 246 general visits made
and a total of 40 visits made to people living with HIV/AIDS. In the last month of the
project, the participants were involved in speaking at a one-week camp meeting which
was held in their community. Two people spoke each day at this event to represent each
of the four focus groups. On the Friday of the camp-meeting, a graduation ceremony was
conducted, and certificates of recognition were issued to the participants. The researcher
was the chief speaker at camp-meeting and 29 people responded to the altar call. The
people coming to the camp-meeting from other churches in the community made requests
to have similar research projects conducted in their churches.
The following are some of the specific results of this intervention. First, this
intervention helped create more peaceful homes. The case in point for this factor is the
couple that were having a dispute but when they were visited by EN, they resolved their
issues and they accepted to go for VCT (see chapter 5).
Secondly, the intervention helped to clarify some of the misunderstanding about
the need for receiving medical attention. This is evidenced by the couple—mentioned in
chapter 5—who had decided not to go to the hospital arguing that God would provide

104
healing in their home. Group D helped this couple to understand that God gives the gift
of healing to be used for his glory. It is not sinning to seek the help of the physicians.
Jesus himself sent lepers to go and be checked by the priests at the temple after receiving
healing. The priests at that time served as physicians.
Thirdly, Nyagiki is experiencing membership church growth. The total
membership (as of May 2018) is 192, up from 171 (as of March 2016). As a result of this
growth, the church facility is not able to accommodate all the people attending the
services. Consequently, the church has made plans of constructing a new church facility
and the work is in progress—the foundation slab has been done and pillars erected, as of
October 2018. The church-sponsored high school has been relocated and its building
facility has been demolished to create room for the church to be built. The capacity of the
new building will be 900 people (the current church can accommodate up to 200 people).
Furthermore, the plan of the new church facility has been modernized to include a
baptismal pool and “flush toilets.” A second fundraiser (in a period of two years) was
conducted on March 10, 2018 where a total of one million Kenyan shillings (US$ 10,000)
was raised. For many church members, this was a divine miracle. The person who was
the chief guest at the fundraiser—a wealthy area politician—voluntarily offered himself
to play that role and has provided a major boost. He came with a team of rich friends and
promised that he was going to provide his truck—free of charge—to transport materials
for building this church and to continue financially supporting this project until it gets
completed. Nyagiki seems to be on fire for God—there is a great revival taking place that
has never been experienced before in her history of over seventy years.

105
Conclusions
To analyze the progression of the research project, I have endeavored to provide
conclusions from previous chapters—chapter 2 through chapter 5. These conclusions will
prepare the way for an overarching conclusion.
Theological Conclusion—Chapter 2
The book of 2 Kings, chapter 5 narrates the story of Naaman who overcame major
obstacles along his way to receive healing. Some of the obstacle he overcame include
Joram (King of Israel) and Gehazi (Elisha’s servant)—both showed violence towards
him. Nevertheless, with the help of his servants and the help of God’s servant (Elisha),
Naaman goes to the River Jordan and after dipping himself seven times, he received
healing. The story of Naaman and Miriam are strong illustrations to dispute the popular
misconception that there was no healing for leprosy in the Old Testament. The Hebrew
word shalom is used to illustrate the total healing that Naaman experienced after dipping
himself in the river Jordan seven times. Healing is complete when it encompasses both
the physical, the mental, and the spiritual (body, mind and spirit) aspects of a human
being. In other words, healing is complete when it is holistic (whole person care).
Another important lesson to learn from Naaman’s healing is that of the role the
laity (church members without professional clergy training) in doing ministry. There is
evidently intentional cooperation between Elisha (clergy) and the servants (laity) of both
Naaman and Elisha. This cooperation should be promoted today in doing ministry
organized by the church and even at the hospital setting. The apostle Peter’s teaching on
priesthood of all believers is very relevant (2 Pet 2:9). The right application of this

106
teaching by the ministers and chaplains will play a bigger role in preventing burnout on
the part of the clergy who love to do ministry alone.
Theoretical Conclusion—Chapter 3
A lot of books were reviewed in preparing for this chapter. I focused on the books
talking about HIV/AIDS in Kenya. The findings indicated that the way the country of
Kenya addressed the issue of HIV/AIDS at its onset was slow, judgmental, and tragic. A
great number of people lost their lives across Kenya (and Africa), people who would be
living today if quick and drastic measures had been taken at the onset. Today, the
churches and faith-based organizations need to work together with the government
agencies to ensure that the gains made so far are scaled up to prevent further spread of
HIV/AIDS in Kenya. Furthermore, both parties can work together to stop social evils—
such as widow inheritance, child prostitution, child labor, and female genital mutilation—
which are associated with the spread of HIV/AIDS. Above all it is worth noting that the
church should not always wait to get the support of the government before acting. Jesus
said that his followers are to be a light in the world and that means that the church should
be at forefront in ministering to the vulnerable population.
Methodological and Implementational
Conclusion—Chapters 4 and 5
The strategy that was used in addressing HIV/AIDS pandemic was very important
in determining good results. In engaging the participants for a period of 18 months, I
utilized concepts from the four educators namely, Malcom Knowles, Jethro, Abraham
Maslow, and Jesus Christ. The research project was carried out in five phases:
Engagement, Exploration, Explanation, Elaboration, and Evaluation. Contextually, using

107
the philosophy of ubuntology was very important: “I am because we are.” In caring for
HIV/AIDS patients, it is beneficial to exercise Ubuntu graces such as empathy,
compassion, and affirmation. It is important to use the right strategy in ministry. The fact
that all 24 participants were enthusiastic and passionate in doing ministry for 18 months
without having anyone drop out could be attributed to the right strategy used in doing
ministry. Ministry, just as in fishing, is successful when the right strategy is used.
Overarching Conclusion
When Jesus saw the crowds, he had compassion on them, for they were like sheep
without a shepherd (Matt 9:36). Jesus—the great physician—is an expert in providing
healing to the sick people. The healing that Jesus provides goes beyond the physical
health of a person. It includes the spiritual, emotional, and psychological aspects of
health. This is evidenced by the example of the forgiveness that he provided to the
paralytic of Capernaum who was brought to Jesus by four men—who made an
impossible thing to happen because of their faith, courage, and determination. White
(1942) says that this person was sick as a result of living a sinful life and the Pharisees
and the doctors of the day had pronounced his condition as incurable and unpardonable
(White, 1942, p. 73). Jesus pronounced spiritual healing to him by saying, “son, your sins
are forgiven” (Mark 2:5). The expectations of many of the people who were present was
for Jesus to provide physical healing, but Jesus provided to him what He thought this
person needed most—spiritual healing. From this experience, we can safely conclude that
for some people, spiritual healing is what they need more than the physical healing. But it
is excellent if they can have both and Jesus is able to do that. Secondly, we need to help
people unconditionally—irrespective of their moral condition.

108
People who are living with HIV/AIDS need help from people who have enough
faith to make impossible things to be possible. Caring for this vulnerable population
requires people who are loving, thoughtful, positive, and kind; people who can see
beyond the valley of dry bones (Dube & Kanyoro, 2004, p. 107). Like Job, people who
know that there is life after the outward skin has been destroyed (Job 19:25-27). Such a
people must be people permanently and intimately connected with Jesus Christ (John
15:5-7; 1 Cor 12:12; Eph 4:15, 16); the ones that Jesus prophesied that they would do
greater things than he did because he was ascending to his father (John 14:12). Such
people are the members of God’s church. God has empowered His church with the power
of the Holy Spirit. The Holy Spirit gives spiritual gifts to the church and one of those
gifts is the gift of healing (1 Cor 12:9). It is therefore without dispute that the church that
relates to Jesus Christ will play a great role in ministering to people living with
HIV/AIDS; just like the servant girl of Naaman and Elisha the prophet, the church will be
a strong agent to point people to Jesus where they will find holistic healing.
Personal Transformation
Tim Sensing (2011) asserts that both the researcher and the participants should
experience transformation in the process of conducting qualitative research
(p. 212). The following are some of lessons that I gained in conducting this research
project.
Empathy versus Sympathy. I have learned to do more for people who are in need
than just showing sympathy (being sorry about what they are experiencing); I have
learned to empathize (doing something to alleviate their suffering) with them. At Nyagiki
I participated in donating an offering to help a lady who desperately needed money to

109
buy a machine to measure her blood pressure daily. I also participated in giving donations
for the new church project.
Social Media Literacy. In this research project, I was able to engage the
participants in “distant learning,” most of my interaction with the participants was by
phone calls, phone conferences, text messages, “What is up,” and by emails. The 21st
century is saturated with a lot of social media that can be used to advance God’s kingdom
and I am passionate about being part of this experience.
Being a Wounded Healer. In January 2017 (In the middle of my research project)
I lost my father—a retired minister who had been a great source of inspiration in my
ministry and career. Family members, friends, and church family members joined
together to provide spiritual and emotional support that I needed to navigate through the
rough waters. I need always to remind myself that I am human and open avenues for
others to care for my needs.
Writing a Book. I would like to write a book dealing with HIV/AIDS that will be
a valuable tool to help church members effectively care for PLWHA from a theological
stand point. This book may be translated into the Swahili language and would benefit
people living in the countries of Eastern Africa—including Kenya.
Developing a Missionary Spirit. When Jesus sent his disciples out on a missionary
journey, he instructed them to travel light and to move forward in faith knowing that God
would provide (Matt 10:9-15; 1 Pet 5:6, 7). Through my sacrificial living—I was
working on a part-time job and getting low income—I was able to make three missionary
journeys without outward sponsorship. In my last journey, I was a guest speaker at the
camp meeting and accepted the arrangement of church members and their pastor to stay

110
in a simple church house (pastor’s residence) where I enjoyed free accommodation and
food. In practicing simplicity, I can save money to return tithe and offering and support
people in need.
Developing Ubuntu Spirit. Serving as a full-time staff chaplain in a big hospital
gives me opportunities to practice ubuntu spirit every day. Some of the things that I do to
express my Ubuntu spirit include: addressing people by their names, applying gentle
touch to people going through misfortune, escorting guests to find their way at the
hospital, sharing greetings and a smile to strangers I meet along the way.
Using my Ministry Opportunities Wisely. One of the 24 research participants died
after a short illness—two months after completing my research project. The person who
died had been an active participant (he was a secretary in one of the focus groups and
faithfully submitted his monthly reports to me). It is true that some of the people I meet
(especially in the hospital setting), I will never have another chance of meeting them.
Therefore, it is crucial that I offer my best care and service. The offer I provide may
make an eternal difference in their lives.
Recommendations
Several recommendations have emerged from the comprehensive analyzes of the
information contained in all the chapters of this research project.
1. After my research study at Nyagiki, several people coming from other
churches requested for similar work to be done in their churches. I therefore recommend
specifically to students and other immigrants coming from the continent of Africa to take
this “Macedonian Call” seriously. The fields are indeed ripe for the harvest, but the
reapers are few (Matt 9:37).

111
2. Chapter 3—Literature Review—disclosed that the situation of HIV/AIDS in
Kenya has been compounded by the presence of such evils as child labor, child
prostitution, widow inheritance, female genital mutilation (FGM). Furthermore, it was
found out that customary laws in Kenya do not permit ladies to inherit land from their
parents/husbands, this situation reduces the financial abilities for ladies causing some of
them to resort to prostitution as a way of getting income. Interventions need to be made
to stop these evil practices.
3. I recommend that Nyagiki church develop an emergency fund to support
PLWHA. This need was voiced by the focus groups. The cost of buying drugs is high and
on top of that they need to eat nutritious foods. Having an emergency fund will be a
brilliant intervention to help meet critical situations like the man who was visited but did
not have money to go to the hospital. The beneficiaries need to be trained on how to raise
their own money to avoid a spirit of dependence. Nyagiki may improvise ways of giving
out clothes and food to the community. This attitude is supported in the Bible (Jas 1:27;
Jas 2:14-17).
4. I recommend to Nyagiki to keep the fire burning. Keep on reaching out to the
communities around the church. Involve more youths and adults to do this work. Short
presentations can be made at church regularly as people gather for their weekly worship
services (on Saturdays). People need to remember that their work in the Lord is not in
vain (1 Cor 15:58; Matt 25:34-40).
5. I recommend to the Nyagiki congregation to keep on reading books to
increase their knowledge on health information. It would be good to have a church library

112
having relevant books on healthful living. Church members—especially the youth—
would greatly appreciate this intervention.
6. Finally, I recommend to the General Conference of the Seventh-day Adventist
Church to distribute the health guidelines to all churches in the world. I read the
guidelines and found them concise and easy to read and understand. These guidelines
were developed back in 1990 but have not been made accessible to its constituent
churches.
A Final Word for Nyagiki
It is very inspiring to see the church’s passion to do ministry and to build a larger
church facility. I believe that once this is completed it will be a beautiful structure on top
of a hill symbolizing the city built on a hill that Jesus told his disciples about (Matt 5:14-
16). In as much as people do not put light under a bushel, do not hide the information—
health information literacy—concerning HIV/AIDS. Allow that light to shine in the
communities brighter and brighter. Please depend on God, continue to embark on this
important journey and be that city set on a hill that glows with light for everyone to see.

